


Product Monograph - Sensipar
SUMMARY PRODUCT INFORMATION
| Route of Administration | Dosage Form/Strength | Clinically Relevant Nonmedicinal Ingredients |
| Oral | Tablet/30 mg, 60 mg, 90 mg | For a complete listing of the nonmedicinal ingredients see Dosage Forms, Composition and Packaging section. |
INDICATIONS AND CLINICAL USE
SENSIPAR (cinacalcet hydrochloride) is indicated for the treatment of secondary hyperparathyroidism (HPT) in patients with Chronic Kidney Disease (CKD) receiving dialysis.
SENSIPAR controls parathyroid hormone levels, calcium and phosphorous levels, and the serum calcium-phosphorous product (Ca x P), in patients with CKD receiving dialysis.
SENSIPAR is indicated for the reduction of hypercalcemia in patients with parathyroid carcinoma.
SENSIPAR is indicated for the reduction of clinically significant hypercalcemia, as defined by relevant treatment guidelines, in patients with primary HPT for whom parathyroidectomy is not clinically appropriate or is contraindicated.
Geriatrics (>65 years of age)
No overall differences in safety and efficacy of SENSIPAR were observed in patients greater or less than 65 years of age (see WARNINGS AND PRECAUTIONS, Special Populations, Geriatrics and DOSAGE AND ADMINISTRATION).
Pediatrics (<18 years of age)
The safety and efficacy of SENSIPAR in pediatric patients have not been established. SENSIPAR is not indicated for use in pediatric patients (see WARNINGS AND PRECAUTIONS, Endocrine and Metabolism, Hypocalcemia and Special Populations, Pediatrics).
CONTRAINDICATIONS
SENSIPAR (cinacalcet hydrochloride) is contraindicated in patients with hypersensitivity to any of the components of this product.
SENSIPAR (cinacalcet hydrochloride) should not be initiated in patients with a serum calcium (corrected for albumin) below the lower limit of the normal range.
For a complete listing of the nonmedicinal ingredients see DOSAGE FORMS, COMPOSITION AND PACKAGING section.
WARNINGS AND PRECAUTIONS
General
Adynamic bone disease may develop if intact parathyroid hormone (iPTH) levels are suppressed below 11.0 pmol/L. If iPTH levels decrease below 11.0 pmol/L in patients receiving dialysis treated with SENSIPAR, the dose of SENSIPAR and/or vitamin D sterols should be reduced or therapy discontinued.
Carcinogenesis and Mutagenesis
SENSIPAR, administered orally for 104 weeks, showed no evidence of carcinogenic potential in mice and rats. Doses administered to mice and rats resulted in total systemic exposure (AUCs) 2 times the exposures observed in humans. The nature, incidence, and distribution of tumours in rats and mice of both sexes did not indicate any SENSIPAR-induced carcinogenesis. A decreased incidence of thyroid C-cell adenomas was observed in rats treated with SENSIPAR.
SENSIPAR was negative in the Ames assay, chromosomal aberration assay, Chinese Hamster Ovary HGPRT forward mutation assay, and in the mouse micronucleus assay. These tests indicate that SENSIPAR has no genetic toxicity either with respect to DNA damage, including gene mutations, large scale chromosomal damage, recombinations or numerical changes.
Cardiovascular
Hypotension and/or Worsening Heart Failure
In post-marketing safety surveillance, idiosyncratic cases of hypotension and/or worsening heart failure have been reported in patients with impaired cardiac function, in which a causal relationship to SENSIPAR could not be completely excluded and may be mediated by reductions in serum calcium levels. Clinical trial data showed hypotension occurred in 7% of SENSIPAR-treated patients, 12% of placebo-treated patients, and heart failure occurred in 2% of patients receiving SENSIPAR or placebo.
QT Prolongation and Ventricular Arrhythmias
Cases of QT prolongation and ventricular arrhythmia secondary to hypocalcemia have been reported in patients treated with SENSIPAR (see WARNINGS AND PRECAUTIONS, Endocrine and Metabolism, Hypocalcemia).
Endocrine and Metabolism
Hypocalcemia
Life-threatening events and fatal outcomes associated with hypocalcemia have been reported in patients treated with SENSIPAR including pediatric patients. SENSIPAR is not indicated for use in pediatric patients (see WARNINGS and PRECAUTIONS, Special Populations, Pediatrics).
SENSIPAR lowers serum calcium, and therefore patients should be carefully monitored for the occurrence of hypocalcemia (see Monitoring and Laboratory Tests). Potential manifestations of hypocalcemia include paresthesias, myalgias, cramping, tetany, and convulsions. Decreases in serum calcium can also prolong the QT interval, potentially resulting in ventricular arrhythmia. Cases of QT prolongation and ventricular arrhythmia secondary to hypocalcemia have been reported in patients treated with SENSIPAR. Caution is advised in patients with other risk factors for QT prolongation such as patients with known congenital long QT syndrome or patients receiving drugs known to cause QT prolongation or lower serum calcium.
SENSIPAR treatment should not be initiated in patients with CKD receiving dialysis if serum calcium is <2.1 mmol/L. If serum calcium falls below 2.1 mmol/L but remains above 1.88 mmol/L or if symptoms of hypocalcemia occur, calcium-containing phosphate binders and/or vitamin D sterols can be used to raise serum calcium. If hypocalcemia or symptoms of QT prolongation/ventricular arrhythmia persist, reduce the dose or discontinue administration of SENSIPAR (see DOSAGE AND ADMINISTRATION).
In CKD patients receiving dialysis who were administered SENSIPAR, 29% of patients had at least one serum calcium value less than 1.88 mmol/L. In a randomized, double-blind, placebo-controlled study in patients with secondary HPT and CKD receiving dialysis, in which patients were treated for up to 64 months (median duration of treatment was 21 months in the SENSIPAR group and 17 months in the placebo group), 21% and 33% of SENSIPAR patients had at least one serum calcium less than 1.88 mmol/L within the first 6 months and overall, respectively (see ADVERSE REACTIONS). In this trial, 1.1% of patients in the SENSIPAR group and 0.1% in the placebo group permanently discontinued study drug due to hypocalcemia.
SENSIPAR is not indicated for CKD patients not receiving dialysis. Investigational studies have shown that SENSIPAR-treated CKD patients not receiving dialysis have an increased risk for hypocalcemia (serum calcium levels < 2.1 mmol/L) compared with SENSIPAR-treated CKD patients receiving dialysis, which may be due to lower baseline calcium levels and/or the presence of residual kidney function.
Testosterone Levels
Testosterone levels are often below the normal range in patients with end stage renal disease. In a clinical study of CKD patients receiving dialysis, free testosterone levels decreased by a median of 31.3% in the SENSIPAR-treated patients and by 16.3% in the placebo-treated patients after 6 months of treatment. The clinical significance of these reductions in serum testosterone is unknown. An open label extension of this study showed no further reductions in free and total testosterone concentrations over a period of 3 years in SENSIPAR-treated patients.
Hepatic
Due to the potential for 2- to 4-fold higher plasma levels of SENSIPAR, patients with moderate to severe hepatic impairment should be closely monitored when initiating treatment (see ACTION AND CLINICAL PHARMACOLOGY).
Malignancies
In a randomized, double-blind, placebo-controlled clinical study of 3,883 CKD patients receiving dialysis, neoplastic events were reported in 2.9 and 2.5 patients per 100 patient-years in the SENSIPAR and placebo-treatment groups, respectively. Serious neoplastic events were reported in 2.0 and 1.8 patients per 100 patient-years, in the SENSIPAR and placebo-treatment groups, respectively. Fatal neoplastic events were reported in 0.6 patients per 100 patient-years for both groups. A causal relationship to SENSIPAR has not been established.
Neurologic
Seizures
In clinical studies, seizures (primarily generalized or tonic-clonic) were observed in 1.4% (43/3049) of SENSIPAR-treated patients and 0.7% (5/687) of placebo-treated patients. While the basis for the reported difference in seizure rate is not clear, the threshold for seizures is lowered by significant reductions in serum calcium levels. Therefore, serum calcium levels should be closely monitored in patients receiving SENSIPAR, particularly in patients with a history of a seizure disorder.
Effect on the Ability to Drive and Use Machines
No effects on the ability to drive or operate machinery have been observed.
Sexual Function / Reproduction
Impairment of Fertility
SENSIPAR had no effect on fertility in animal studies.
Special Populations
Pregnant Women
There are no studies on the use of SENSIPAR in pregnant women. SENSIPAR was not teratogenic in rabbits when given a dose of 0.4 times, on an area under the curve (AUC) basis, the maximum human dose for secondary HPT (180 mg once daily). There were no effects on fertility in males or females at exposures up to 4 times a human dose of 180 mg/day. In pregnant rats, there were slight decreases in body weight and food consumption at the highest dose. The non-teratogenic dose in rats was 4.4 times, on an AUC basis, the maximum dose for patients with secondary HPT (180 mg once daily). Decreased fetal weights were seen in rats at doses where dams had severe hypocalcemia. SENSIPAR has been shown to cross the placental barrier in rabbits. Although animal studies have shown no evidence of teratogenicity, SENSIPAR should be used during pregnancy only if the potential benefit justifies the potential risk to the fetus.
Nursing Women
It is not known whether SENSIPAR is excreted in human milk. Studies in rats have shown that SENSIPAR is excreted in the milk with a high milk to plasma ratio. A decision should be made whether to discontinue nursing or discontinue SENSIPAR, taking into account the importance of SENSIPAR to the mother.
Pediatrics (<18 years of age)
The safety and efficacy of SENSIPAR in pediatric patients have not been established. SENSIPAR is not indicated for use in pediatric patients.
A fatal outcome was reported in a pediatric clinical trial patient with severe hypocalcemia (see WARNINGS and PRECAUTIONS, Endocrine and Metabolism, Hypocalcemia).
Geriatrics (>65 years of age)
Of the 1136 patients enrolled in the SENSIPAR phase 3 clinical program, 26% were > 65 years old, while 9% were > 75 years old. No overall differences in safety and efficacy of SENSIPAR were observed in patients greater or less than 65 years of age (see DOSAGE AND ADMINISTRATION).
Monitoring and Laboratory Tests
Patients with CKD and Secondary Hyperparathyroidism
Serum calcium should be measured within 1 week and iPTH should be measured 1 to 4 weeks after initiation or dose adjustment of SENSIPAR. Once the maintenance dose levels have been established, serum calcium and serum phosphorus should be measured approximately monthly, and PTH (iPTH) every 1 to 3 months (see DOSAGE AND ADMINISTRATION). Either the intact PTH (iPTH) or bio-active PTH (biPTH) may be used to measure plasma PTH levels. Treatment with SENSIPAR does not alter the relationship between iPTH and biPTH.
ADVERSE REACTIONS
Adverse Drug Reaction Overview
Studies were conducted in patients with secondary hyperparathyroidism (HPT) and Chronic Kidney Disease (CKD) receiving dialysis, parathyroid carcinoma or primary HPT. SENSIPAR (cinacalcet hydrochloride) was safe and generally well tolerated.
Hypocalcemia
SENSIPAR lowers serum calcium, and therefore patients should be carefully monitored for the occurrence of hypocalcemia (see Monitoring and Laboratory Tests). Potential manifestations of hypocalcemia include paresthesias, myalgias, cramping, tetany, and convulsions. Decreases in serum calcium can also prolong the QT interval, potentially resulting in ventricular arrhythmia. Cases of QT prolongation and ventricular arrhythmia secondary to hypocalcemia have been reported in patients treated with SENSIPAR. Caution is advised in patients with other risk factors for QT prolongation such as patients with known congenital long QT syndrome or patients receiving drugs known to cause QT prolongation or lower serum calcium (see WARNINGS AND PRECAUTIONS).
Clinical Trial Adverse Drug Reactions
Because clinical trials are conducted under very specific conditions the adverse reaction rates observed in the clinical trials may not reflect the rates observed in practice and should not be compared to the rates in the clinical trials of another drug. Adverse drug reaction information from clinical trials is useful for identifying drug-related adverse events and for approximating rates.
Secondary Hyperparathyroidism in Patients with CKD Receiving Dialysis
In three double-blind placebo-controlled clinical trials, 1126 CKD patients receiving dialysis received study drug (656 SENSIPAR, 470 placebo) for up to six months. Adverse events reported during the studies were typical for the dialysis patient population. The most frequently reported adverse events (incidence of at least 5% in the SENSIPAR-treated group) are provided in Table 1. The most frequently reported events in the SENSIPAR group were nausea and vomiting which were generally mild to moderate in severity, brief in duration, and infrequently led to discontinuation of study drug.
Table 1. Adverse Event Incidence (≥ 5%) in Patients Receiving Dialysis
| Placebo | SENSIPAR | |
| (n = 470) | (n = 656) | |
| Preferred Term | % | % |
| Nausea | 19 | 31 |
| Vomiting | 15 | 27 |
| Diarrhea | 20 | 21 |
| Headache | 17 | 16 |
| Myalgia | 14 | 15 |
| Pain Abdominal | 14 | 12 |
| Infection Upper Respiratory | 13 | 12 |
| Dizziness | 8 | 10 |
| Dyspnea | 9 | 9 |
| Pain Limb | 10 | 9 |
| Dyspepsia | 8 | 8 |
| Arthralgia | 9 | 7 |
| Fever | 10 | 7 |
| Fatigue | 7 | 7 |
| Hypertension | 5 | 7 |
| Hypotension | 12 | 7 |
| Edema Peripheral | 7 | 7 |
| Asthenia | 4 | 7 |
| Cough | 7 | 6 |
| Pruritus | 7 | 6 |
| Anorexia | 4 | 6 |
| Thrombosis Vascular Access | 7 | 6 |
| Pain Chest, Non-Cardiac | 4 | 6 |
| Access Infection | 4 | 5 |
The incidence of serious adverse events (29% vs 31%) and deaths (2% vs 3%) was similar in the SENSIPAR and placebo groups, respectively.
Seizures were observed in 1.4% (13/910) of SENSIPAR-treated patients and 0.7% (5/641) of placebo-treated patients across all completed placebo-controlled trials.
Seizures were observed in 1.2% (8/656) of SENSIPAR-treated patients and 0.4% (2/470) of placebo-treated patients in the three double-blind placebo-controlled clinical trials in CKD patients receiving dialysis (see WARNINGS AND PRECAUTIONS).
12-Month Experience with SENSIPAR in Secondary Hyperparathyroidism
Two hundred sixty-six patients from the two pivotal phase 3 studies continued to receive SENSIPAR or placebo treatment in a 6-month double-blind extension study (12-month total treatment duration). The incidence and nature of adverse events in this study were similar in the two treatment groups, and comparable to those observed in the pivotal phase 3 studies.
Parathyroid Carcinoma and Primary Hyperparathyroidism (HPT)
One hundred sixty patients with primary HPT or parathyroid carcinoma participated in SENSIPAR clinical trials with exposure for up to 5.5 years.
The safety profile of SENSIPAR in these patient populations is generally consistent with that seen in patients with CKD receiving dialysis. The most frequent adverse drug reactions in these patient populations were nausea and vomiting.
Seizures were observed in 0.7% (1/140) of SENSIPAR-treated patients and 0% (0/46) of placebo-treated patients in the clinical trials in patients with primary HPT or parathyroid carcinoma (see WARNINGS AND PRECAUTIONS).
Laboratory Values
Serum calcium levels should be monitored in patients receiving SENSIPAR (see WARNINGS AND PRECAUTIONS and DOSAGE AND ADMINISTRATION). In the three phase 3 studies in patients with CKD receiving dialysis, 29% of patients receiving SENSIPAR had at least one serum calcium value < 1.88 mmol/L. In a randomized, double-blind, placebo-controlled study in patients with secondary HPT and CKD receiving dialysis, in which patients were treated for up to 64 months (median duration of treatment was 21 months in the SENSIPAR group and 17 months in the placebo group), 21% and 33% of SENSIPAR patients had at least one serum calcium less than 1.88 mmol/L within the first 6 months and overall, respectively.
Post-Market Adverse Drug Reactions
Additional adverse events have been identified during post-marketing use of SENSIPAR. These adverse events include, but are not limited to, the following (listed by body system):
| Cardiac disorders: | hypotension, worsening heart failure, QT prolongation and ventricular arrhythmia secondary to hypocalcemia |
| Gastrointestinal disorders: | abdominal pain upper, constipation |
| Immune system disorders: | hypersensitivity reactions (including angioedema and urticaria), severe hypersensitivity reaction |
| Metabolism and nutrition disorders: | hypocalcemia (some cases with fatal outcomes), hyperkalemia |
| Musculoskeletal and connective tissue disorders: | back pain, muscle spasms, calcium pyrophosphate deposition (CPPD; pseudogout) |
| Skin and subcutaneous tissue disorders: | rash |
DRUG INTERACTIONS
Drug-Drug Interactions
Effect of SENSIPAR on other drugs
Drugs metabolized by CYP450 2D6: SENSIPAR (cinacalcet hydrochloride) is an inhibitor of CYP2D6. Therefore, dose adjustments of concomitant medications that are predominantly metabolized by CYP2D6 (eg, metoprolol) and particularly those with a narrow therapeutic index (eg, flecainide, vinblastine, thioridazine and most tricyclic antidepressants) may be required.
Desipramine: Concurrent administration of 90 mg SENSIPAR with 50 mg desipramine, a tricyclic antidepressant metabolized primarily by CYP2D6, increased desipramine exposure by approximately 3.6-fold in CYP2D6 extensive metabolizers.
Amitriptyline: Concurrent administration of 25 mg or 100 mg SENSIPAR with 50 mg amitriptyline, a tricyclic antidepressant metabolized in part by CYP2D6, increased exposure to amitriptyline and its active metabolite nortriptyline by approximately 20% in extensive metabolizers of CYP2D6 enzymes. Dose reductions of amitriptyline may be required in some subjects receiving SENSIPAR concurrently.
Drugs metabolized by other CYP enzymes
Based on in vitro data, SENSIPAR is not an inhibitor of other CYP enzymes at concentrations achieved clinically, including CYP1A2, CYP2C9, CYP2C19, and CYP3A4. In vitro studies indicate that SENSIPAR is not an inducer of CYP1A2, CYP2C19 and CYP3A4.
Midazolam: Co-administration of SENSIPAR (90 mg) with orally administered midazolam (2 mg), a CYP3A4 and CYP3A5 substrate, did not alter the pharmacokinetics of midazolam. These data suggest that SENSIPAR would not affect the pharmacokinetics of those classes of drugs that are metabolized by CYP3A4 and CYP3A5, such as certain immunosuppressants, including cyclosporine and tacrolimus.
Warfarin: SENSIPAR does not affect the pharmacokinetics or pharmacodynamics (as measured by prothrombin time and clotting factor VII) of warfarin.
The lack of effect of SENSIPAR on the pharmacokinetics of R and S warfarin and the absence of auto induction upon multiple dosing in patients indicates that SENSIPAR is not an inducer of CYP3A4, CYP1A2 or CYP2C9 in humans.
Effect of other drugs on SENSIPAR
SENSIPAR is metabolized by multiple cytochrome P450 enzymes, primarily CYP3A4 and CYP1A2, which limits the potential for other drugs to increase cinacalcet concentrations.
Ketoconazole: SENSIPAR is metabolized in part by the enzyme CYP3A4. Co-administration of 200 mg bid of ketoconazole, a strong inhibitor of CYP3A4, caused an approximate 2-fold increase in cinacalcet exposure. Dose adjustment of SENSIPAR may be required if a patient initiates or discontinues therapy with a strong CYP3A4 inhibitor (eg, ketoconazole, erythromycin, itraconazole) or inducer (eg, rifampin, phenytoin) of this enzyme.
Calcium carbonate: Co-administration of calcium carbonate (single 1500 mg dose) did not alter the pharmacokinetics of SENSIPAR.
Pantoprazole: Co-administration of pantoprazole (80 mg qd) did not alter the pharmacokinetics of SENSIPAR.
Sevelamer HCl: Co-administration of sevelamer HCl (2400 mg tid) did not alter the pharmacokinetics of SENSIPAR.
Drug-Food Interactions
After oral administration of SENSIPAR (cinacalcet hydrochloride), maximum plasma concentration is achieved in approximately 2 to 6 hours. Administration of SENSIPAR with food results in an approximate 50 to 80% increase in bioavailability. Increases in plasma concentration are similar, regardless of the fat content of the meal.
Drug-Herb Interactions
Interactions with herbal products have not been established.
Drug-Laboratory Test Interactions
Interactions with laboratory tests have not been established.
DOSAGE AND ADMINISTRATION
SENSIPAR (cinacalcet hydrochloride) can be used alone or in combination with vitamin D sterols and/or phosphate binders.
SENSIPAR (cinacalcet hydrochloride) is administered orally. Tablets should be taken whole and should not be chewed, crushed, or divided. Take SENSIPAR with food or shortly after a meal (see DRUG INTERACTIONS).
Secondary Hyperparathyroidism in Patients with Chronic Kidney Disease (CKD) Receiving Dialysis
The recommended starting oral dose of SENSIPAR is 30 mg once daily. SENSIPAR should be titrated every 2 to 4 weeks to a maximum dose of 180 mg once daily to achieve a target PTH between 1.5 to 5 times the upper limit of normal.
In CKD patients, PTH levels should be assessed at least 12 hours after dosing with SENSIPAR.
Low serum calcium levels should be corrected before initiating therapy (see WARNINGS and PRECAUTIONS, Endocrine and Metabolism, Hypocalcemia).
During dose titration, serum calcium levels should be monitored frequently and if serum calcium levels decrease below the normal range, appropriate steps should be taken to increase serum calcium levels (see WARNINGS AND PRECAUTIONS). Calcium levels should be corrected for albumin or ionized calcium levels should be measured.
Parathyroid Carcinoma and Primary Hyperparathyroidism (HPT)
The recommended starting dose of SENSIPAR for adults is 30 mg twice per day.
The dosage of SENSIPAR should be titrated sequentially every 2 to 4 weeks through dosages of 30 mg twice daily, 60 mg twice daily, and 90 mg twice daily to reduce serum calcium levels. For further information on higher dosages (90 mg 3 or 4 times daily) see CLINICAL TRIALS: Parathyroid Carcinoma and Primary HPT for Whom Parathyroidectomy is not a Treatment Option.
Special Populations
Geriatric patients
Age does not alter the pharmacokinetics of SENSIPAR; no dose adjustment is required for geriatric patients.
Patients with renal impairment
Renal impairment does not alter the pharmacokinetics of SENSIPAR; no dosage adjustment is necessary for renal impairment.
Patients with hepatic impairment
Moderate to severe hepatic impairment (Child-Pugh classification) increases SENSIPAR drug concentrations by approximately 2- to 4-fold. In patients with moderate-severe hepatic impairment, PTH and serum calcium concentrations should be closely monitored during dose titration of SENSIPAR.
OVERDOSAGE
Doses titrated up to 300 mg once daily have been safely administered to patients receiving dialysis. Overdosage of SENSIPAR (cinacalcet hydrochloride) may lead to hypocalcemia. In the event of overdosage, patients should be monitored for signs and symptoms of hypocalcemia and appropriate measures taken to correct serum calcium levels (see WARNINGS AND PRECAUTIONS).
Since SENSIPAR is highly protein bound, hemodialysis is not an effective treatment for overdosage of SENSIPAR.
| For management of a suspected drug overdose, contact your regional Poison Control Centre. |
ACTION AND CLINICAL PHARMACOLOGY
Mechanism of Action
Secondary hyperparathyroidism is a progressive disease, which occurs in patients with chronic kidney disease and manifests as increases in parathyroid hormone levels and derangements in calcium and phosphorous metabolism. Increased PTH stimulates osteoclastic activity resulting in cortical bone resorption and marrow fibrosis. The calcium-sensing receptor on the surface of the chief cell of the parathyroid gland is the principal regulator of PTH secretion. Cinacalcet hydrochloride directly lowers PTH levels by increasing the sensitivity of the calcium-sensing receptor to extracellular calcium. The reduction in PTH is associated with a concomitant decrease in serum calcium levels.
Pharmacodynamics
Reduction in iPTH levels is correlated with cinacalcet concentration. The nadir in iPTH level occurs approximately 2 to 6 hours post dose, corresponding with the Cmax of cinacalcet. After steady state is reached, serum calcium concentrations remain constant over the dosing interval.
Pharmacokinetics
Absorption and Distribution
After oral administration of SENSIPAR, maximum plasma concentration is achieved in approximately 2 to 6 hours. The absolute bioavailability of cinacalcet is approximately 25%. Administration of SENSIPAR with food results in an approximate 50 to 80% increase in bioavailability. Increases in plasma concentrations are similar regardless of the fat content of the meal.
After absorption, cinacalcet concentrations decline in a biphasic fashion with an initial half-life of approximately 6 hours and a terminal half-life of 30 to 40 hours. Steady state drug levels are achieved within 7 days with minimal accumulation. The AUC and Cmax of cinacalcet increase linearly over the dose range of 30 to 180 mg once daily. The pharmacokinetics of cinacalcet does not change over time. The volume of distribution is high (approximately 1000 L), indicating extensive distribution. Cinacalcet is approximately 97% bound to plasma proteins and distributes minimally into red blood cells.
Metabolism and Excretion
Cinacalcet is metabolized by multiple enzymes, primarily CYP3A4 and CYP1A2. The major circulating metabolites are inactive. After administration of a 75 mg radio-labeled dose to healthy volunteers, cinacalcet was rapidly and extensively metabolized by oxidation followed by conjugation. Renal excretion of metabolites was the prevalent route of elimination of radioactivity. Approximately 80% of the dose was recovered in the urine and 15% in the feces.
Special Populations and Conditions
Geriatric Patients
The pharmacokinetics of SENSIPAR are similar in patients greater than, or less than, 65 years of age. No dosage adjustment based on age is necessary.
Pediatric Patients
The pharmacokinetics of SENSIPAR have not been studied in patients < 18 years of age (see WARNINGS AND PRECAUTIONS).
Hepatic Insufficiency
Mild hepatic impairment did not notably affect the pharmacokinetics of SENSIPAR. Compared to subjects with normal liver function, average AUC of cinacalcet was approximately 2-fold higher in subjects with moderate impairment and approximately 4-fold higher in subjects with severe impairment (see WARNINGS AND PRECAUTIONS). Because doses are titrated for each subject based on safety and efficacy parameters, no additional dose adjustment is necessary for subjects with hepatic impairment.
Renal Insufficiency
The pharmacokinetic profile of SENSIPAR in patients with mild, moderate, and severe renal insufficiency, and those on hemodialysis or peritoneal dialysis is comparable to that in healthy volunteers. No dosage adjustment based on renal function is necessary.
STORAGE AND STABILITY
Store at 15ºC to 30ºC. Keep in a safe place out of the reach and sight of children.
DOSAGE FORMS, COMPOSITION AND PACKAGING
SENSIPAR (cinacalcet hydrochloride) tablets are composed of cinacalcet hydrochloride, pre-gelatinized starch, microcrystalline cellulose, povidone, crospovidone, colloidal silicon dioxide, magnesium stearate, and water. Tablets are coated with colour (Opadry® II green), clear film-coat (Opadry® clear), and carnauba wax.
SENSIPAR 30 mg tablets are formulated as light green, film-coated, oval-shaped tablets marked with “AMG” on one side and “30” on the opposite side, packaged in bottles of 30 tablets.
SENSIPAR 60 mg tablets are formulated as light green, film-coated, oval-shaped tablets marked with “AMG” on one side and “60” on the opposite side, packaged in bottles of 30 tablets.
SENSIPAR 90 mg tablets are formulated as light green, film-coated, oval-shaped tablets marked with “AMG” on one side and “90” on the opposite side, packaged in bottles of 30 tablets.
PART II: SCIENTIFIC INFORMATION
PHARMACEUTICAL INFORMATION
Drug Substance
| Proper name: | cinacalcet hydrochloride |
| Chemical name: | N-[1-(R)-(1-naphthyl)ethyl]-3-[3-(trifluoromethyl)phenyl]-1-aminopropane hydrochloride |
| Molecular weight: | 393.9 g/mol (hydrochloride salt), 357.4 g/mol (free base) |
| Structural formula: | 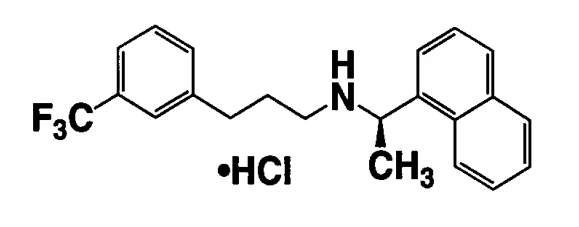 |
| Physicochemical properties: | |
| Physical Form: | White to off white crystalline powder |
| Solubility: | Slightly soluble in water and in acetonitrile; freely soluble in methanol, ethanol, methylene chloride, and chloroform; very slightly soluble in hexane; sparingly soluble in isopropyl alcohol |
| pH: | 5.1 |
| pKa: | 8.72 |
| Partition coefficient (octanol:water): | 4.79:log P |
| Melting Point: | 178°C to 184°C |
CLINICAL TRIALS
Secondary Hyperparathyroidism in Patients with Chronic Kidney Disease Receiving Dialysis
Three, 6-month, multicenter, randomized, double-blind, placebo-controlled clinical studies were conducted in CKD patients receiving dialysis with uncontrolled secondary HPT (n = 1136). The patient population consisted of both recently established and long-standing dialysis patients, with a duration of dialysis treatment that ranged from 1 to 359 months. SENSIPAR (cinacalcet hydrochloride) was administered either alone or in combination with vitamin D sterols; 34% of patients were not receiving vitamin D sterols at study entry. The majority (> 90%) of patients were receiving phosphate binders. Dose adjustments in phosphate binder therapy were permitted throughout the study. Vitamin D doses remained constant unless the patient developed hypercalcemia, hypocalcemia, or hyperphosphatemia. Patients continued on their previously prescribed drugs including: calcium channel blockers, ACE inhibitors, beta-blockers, hypoglycemics, and lipid lowering agents. SENSIPAR (or placebo) was initiated at a dose of 30 mg and titrated every 3 or 4 weeks to a maximum dose of 180 mg once daily to achieve an iPTH of 11 to 27.5 pmol/L (1.5 to 4 times the upper limit of normal). The severity of secondary HPT ranged from mild to severe (iPTH values of 29.8 to 1005.2 pmol/L), with mean (SE) baseline iPTH concentrations across the three studies of 78 (2.2) and 72 (2.0) pmol/L for the SENSIPAR and placebo groups, respectively. Significant reductions in iPTH, serum calcium-phosphorus product (Ca x P), calcium, and phosphorus were observed in the SENSIPAR-treated patients compared with placebo-treated patients receiving standard of care, and the results were consistent across the three studies (Table 2). Mean iPTH and Ca x P by treatment group for the overall study population during the 6-month treatment period are presented in Figures 1 and 2.
Table 2. Effects of SENSIPAR on iPTH, Ca x P, Serum Calcium, and Serum Phosphorus in 6-month Phase 3 Studies (Patients Receiving Dialysis)
| Study 1 | Study 2 | Study 3 | ||||||||||||||||||||
| Placebo | SENSIPAR | Placebo | SENSIPAR | Placebo | SENSIPAR | |||||||||||||||||
| (n = 205) | (n = 205) | (n = 165) | (n = 166) | (n = 101) | (n = 294) | |||||||||||||||||
| iPTH | ||||||||||||||||||||||
| Baseline (pmol/L) | 69 (2.9) | 67 (2.5) | 67 (2.5) | 69 (3.1) | 88 (5.1) | 90 (4.3) | ||||||||||||||||
| Evaluation Phase (pmol/L) | 74 (3.5) | 41 (2.6) | 73 (3.4) | 38 (3.1) | 90 (5.8) | 56 (3.2) | ||||||||||||||||
| Percent Change | 9.5 (2.8) | -38.4 (2.9) | 8.7 (2.8) | -47.5 (2.8) | 4.1 (3.4) | -40.3 (2.1) | ||||||||||||||||
| Patients Achieving Primary Endpoint (iPTH ≤ 250 pg/mL; 27.5 pmol/L) (%) | 4% | 41%** | 7% | 46%** | 6% | 35%** | ||||||||||||||||
| Patients Achieving ≥ 30% Reduction in iPTH (%) | 11% | 61%** | 12% | 68%** | 10% | 59%** | ||||||||||||||||
| Patients Achieving iPTH ≤ 300 pg/mL; (33 pmol/L) (%) | 9% | 55%** | 11% | 56%** | 9% | 45%** | ||||||||||||||||
| Ca x P | ||||||||||||||||||||||
| Baseline (mmol2/L2) | 4.9 (0.09) | 5 (0.09) | 4.9 (0.01) | 4.9 (0.01) | 4.9 (0.11) | 4.8 (0.08) | ||||||||||||||||
| Evaluation Phase (mmol2/L2) | 4.8 (0.08) | 4.2 (1.0) | 4.8 (0.01) | 4.0 (0.10) | 4.7 (0.10) | 4.0 (0.07) | ||||||||||||||||
| Percent Change | 1.5 (1.8) | -13.0 (1.7)** | -0.7 (1.9) | -16.7 (2.1)** | -1.4 (2.4) | -12.8 (1.7)** | ||||||||||||||||
| Calcium | ||||||||||||||||||||||
| Baseline (mmol/L) | 2.48 (0.025) | 2.45 (0.025) | 2.48 (0.025) | 2.5 (0.025) | 2.5 (0.025) | 2.45 (0.0125) | ||||||||||||||||
| Evaluation Phase (mmol/L) | 2.48 (0.025) | 2.3 (0.025) | 2.48 (0.025) | 2.3 (0.025) | 2.5 (0.025) | 2.28 (0.025) | ||||||||||||||||
| Percent Change | 0.5 (0.3) | -6.3 (0.6)** | 0.3 (0.4) | -7.5 (0.6)** | 0.9 (0.5) | -6.5 (0.6)** | ||||||||||||||||
| Phosphorus | ||||||||||||||||||||||
| Baseline (mmol/L) | 2 (0.032) | 2.03 (0.032) | 2 (0.032) | 1.97 (0.1) | 1.97 (0.032) | 1.97 (0.032) | ||||||||||||||||
| Evaluation Phase (mmol/L) | 1.94 (0.032) | 1.84 (0.032) | 1.94 (0.1) | 1.74 (0.032) | 1.87 (0.032) | 1.78 (0.032) | ||||||||||||||||
| Percent Change | 1.1 (1.8) | -7.1 (1.7)** | -0.9 (1.9) | -9.9 (2.0)** | -2.2 (2.5) | -7.2 (1.6)* | ||||||||||||||||
* p < 0.05; ** p < 0.001 compared to placebo
Figure 1. Mean (SE) Percent Change from Baseline in iPTH (Pooled Phase 3 Studies)
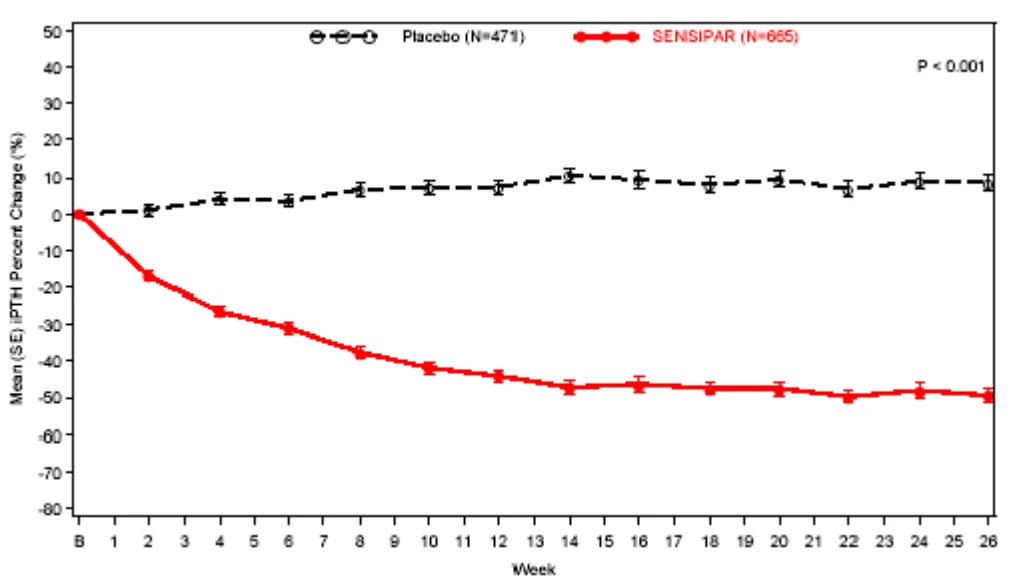
Figure 2. Mean (SE) Percent Change from Baseline in Ca x P (Pooled Phase 3 Studies)
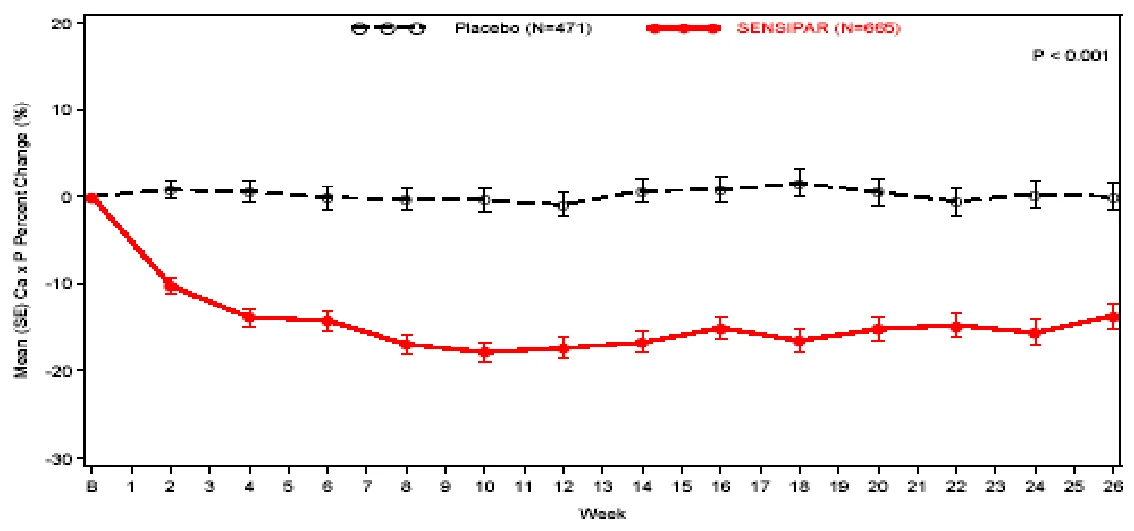
Reductions in iPTH and Ca x P occurred within 2 weeks and were maintained for up to 12 months of treatment. SENSIPAR decreased iPTH and Ca x P levels regardless of disease severity (ie, baseline iPTH value), dialysis modality (PD versus HD), duration of dialysis, and whether or not vitamin D sterols were administered. Approximately 60% of patients with mild (iPTH ≥ 33 to ≤ 55 pmol/L), moderate (iPTH > 55 to 88 pmol/L), or severe (iPTH > 88 pmol/L) secondary HPT achieved a ≥ 30% reduction in iPTH levels. SENSIPAR treatment reduced iPTH and Ca x P regardless of pre-treatment Ca x P levels.
Bone Health
In CKD patients with uncontrolled secondary HPT, reductions in PTH were associated with a favourable impact on bone specific alkaline phosphatase (BALP), N-telopeptide (N-Tx), bone turnover, bone fibrosis, and incidence of bone fracture.
Cardiovascular
A randomized, double-blind placebo-controlled study of 3,883 patients with secondary HPT and CKD receiving dialysis, evaluated SENSIPAR vs. placebo for the reduction of the risk of all-cause mortality and cardiovascular events. The study did not meet its primary objective of demonstrating a reduction in risk of all-cause mortality or cardiovascular events including myocardial infarction, hospitalization for unstable angina, heart failure or peripheral vascular event (HR 0.93; 95% CI: 0.85, 1.02; p = 0.112).19
Parathyroid Carcinoma and Primary HPT for Whom Parathyroidectomy is not a Treatment Option
Forty-six patients participated in the clinical trial supporting the indications in patients with parathyroid carcinoma (29 patients) and primary HPT who had failed or had contraindications to surgery (17 patients), ie, for whom parathyroidectomy is not a treatment option. Patients were treated for as long as 3 years. The mean duration of follow-up was 328 days for patients with parathyroid carcinoma and 347 days for patients with primary HPT. SENSIPAR was administered at dosages ranging from 30 mg twice daily to 90 mg four times daily (13 patients received the 90 mg four times daily dosage). The primary endpoint of the study was a reduction of serum calcium of ≥ 1 mg/dL (0.25 mmol/L). Eighteen of 29 patients (62%) with parathyroid carcinoma and 15 of 17 patients (88%) with primary HPT achieved a reduction of serum calcium of ≥ 1 mg/dL (0.25 mmol/L). In patients with parathyroid carcinoma, mean serum calcium declined from 14.1 mg/dL at baseline to 12.4 mg/dL (3.5 mmol/L to 3.1 mmol/L) at the end of the titration phase (up to 16 weeks). In patients with primary HPT, serum calcium levels declined from 12.7 mg/dL at baseline to 10.4 mg/dL (3.2 mmol/L to 2.6 mmol/L) at the end of the titration phase (up to 16 weeks).
DETAILED PHARMACOLOGY
Preclinical Studies
Studies in a rat model of chronic renal insufficiency (CRI; 5/6 nephrectomy) assessed the effects of cinacalcet (HCl) treatment on parathyroid gland hyperplasia. Cinacalcet HCl treatment reduced intact PTH (iPTH) and parathyroid cell proliferation to levels comparable to vehicle treated, non-nephrectomized animals, demonstrating that cinacalcet HCl prevented the development of secondary HPT.
REFERENCES
- 1. Bilezikian JP. Management of acute hypercalcemia. N Engl J Med. 326:1196-1203 1992.
- 2. Block G, Port FK. Calcium phosphate metabolism and cardiovascular disease in patients with chronic kidney disease. Semin Dial. 16(2):140-7 2003.
- 3. Block GA, Hulbert-Shearon TE, Levin NW, Port FK. Association of serum phosphorus and calcium x phosphate product with mortality risk in chronic hemodialysis patients: A national study. Am J Kidney Dis. 31:607-617 1998.
- 4. Block GA, Martin KJ, de Francisco ALM, et al. Cinacalcet for Secondary Hyperparatyroidism in Patients Receiving Hemodialysis. N Engl J Med 350;15:1516-1525, 2004.
- 5. Block GA, Port FK. Re-evaluation of risks associated with hyperphosphatemia and hyperparathyroidism in dialysis patients: Recommendations for a change in management. Am J Kidney Dis. 35:1226-1237 2000.
- 6. Coburn JW, Maung HM. Calcimimetic agents and the calcium-sensing receptor. Curr Opin Nephrol Hypertens. 9(2):123-32 2000.
- 7. de Boer IH, Gorodetskaya I, Young B, Hsu CY, Chertow GM. The severity of secondary hyperparathyroidism in chronic renal insufficiency is GFR-dependent, race-dependent, and associated with cardiovascular disease. J Am Soc Nephrol. 13(11):2762-9 2002.
- 8. Drueke TB. The pathogenesis of parathyroid gland hyperplasia in chronic renal failure. Kidney Int. 48(1):259-72 1995.
- 9. Ganesh SK, Stack AG, Levin NW, Hulbert-Shearon T, Port FK. Association of elevated serum PO4, Ca x P product, and parathyroid hormone with cardiac mortality risk in chronic hemodialysis patients. J Am Soc Nephrol. 12:2131-2138 2001.
- 10. Goodman WG. Recent developments in the management of secondary hyperparathyroidism. Kidney Int. 59(3):1187-1201 2001.
- 11. Jones CA, McQuillan GM, Kusek JW, et al. Serum creatinine levels in the US population: third National Health and Nutrition Examination Survey. Am J Kidney Dis 1998;32:992-999.
- 12. Nemeth EF, Bennett SA. Tricking the parathyroid gland with novel calcimimetic agents. Nephrology Dialysis Transplantation. 13(8):1923-1925 1998.
- 13. Peacock M, Bilezikian JP, Klassen PS, et al. Cinacalcet hydrochloride maintains long-term normocalcemia in patients with primary hyperparathyroidism. J Clin Endocrinol Metab. 90(1):135-141, 2005.
- 14. Quarles LD. Extracellular calcium-sensing receptors in the parathyroid gland, kidney, and other tissues. Curr Opin Nephrol Hypertens. Jul;12(4):349-55 2003.
- 15. Rostand SG, Drueke TB. Parathyroid hormone, vitamin D, and cardiovascular disease in chronic renal failure. Kidney Int. 56:383-392 1999.
- 16. Silverberg SJ, Rubin MR, Faiman C, et al. Cinacalcet hydrochloride reduces the serum calcium concentration in inoperable parathyroid carcinoma. J Clin Endocrinol Metab.92(10):3803-3808, 2007.
- 17. Slatopolsky E, Brown A, Dusso A. Pathogenesis of secondary hyperparathyroidism. Kidney Intl. 56:S14-S19 1999.
- 18. Spasovski GB, Bervoets ARJ, Behets GJS, et al. Spectrum of renal bone disease in end-stage renal failure patients not yet on dialysis. Nephrol Dial Transplan. 18:1159-1166, 2003.
- 19. The EVOLVE Trial Investigators. Effect of cinacalcet on cardiovascular disease in patients undergoing dialysis. N Engl J Med. 367:2482-2494, 2012.
- 20. United States Renal Data System. USRDS 2002 Annual Data Report: Atlas of End-Stage Renal Disease in the United States. Bethesda, MD: National Institutes of Health, National Institute of Diabetes and Digestive and Kidney Diseases; 2002.