


Product Monograph - Stromectol
RECENT MAJOR LABEL CHANGES
| 7 WARNINGS AND PRECAUTIONS | 10/2021 |
TABLE OF CONTENTS
Sections or subsections that are not applicable at the time of authorization are not listed.
RECENT MAJOR LABEL CHANGES............................................................................................ 2
TABLE OF CONTENTS .............................................................................................................. 2
PART I: HEALTH PROFESSIONAL INFORMATION ..................................................................... 4
1 INDICATIONS .............................................................................................................. 4
1.1 Pediatrics .......................................................................................................... 4
1.2 Geriatrics........................................................................................................... 4
2 CONTRAINDICATIONS ................................................................................................. 4
4 DOSAGE AND ADMINISTRATION................................................................................. 4
4.1 Dosing Considerations ....................................................................................... 4
4.2 Recommended Dose and Dosage Adjustment..................................................... 4
4.4 Administration................................................................................................... 6
4.5 Missed Dose ...................................................................................................... 6
5 OVERDOSAGE ............................................................................................................. 6
6 DOSAGE FORMS, STRENGTHS, COMPOSITION AND PACKAGING ................................. 6
7 WARNINGS AND PRECAUTIONS .................................................................................. 6
7.1 Special Populations ............................................................................................ 8
7.1.1 Pregnant Women ......................................................................................... 8
7.1.2 Breast-feeding.............................................................................................. 8
7.1.3 Pediatrics ..................................................................................................... 8
7.1.4 Geriatrics ..................................................................................................... 8
8 ADVERSE REACTIONS .................................................................................................. 8
8.1 Adverse Reaction Overview................................................................................ 8
8.2 Clinical Trial Adverse Reactions .......................................................................... 8
8.4 Abnormal Laboratory Findings: Hematologic, Clinical Chemistry and Other Quantitative Data ...................................................................................................... 10
8.5 Post-Market Adverse Reactions........................................................................ 10
9 DRUG INTERACTIONS................................................................................................ 10
9.2 Drug Interactions Overview.............................................................................. 10
9.4 Drug-Drug Interactions .................................................................................... 10
9.5 Drug-Food Interactions .................................................................................... 11
9.6 Drug-Herb Interactions .................................................................................... 11
9.7 Drug-Laboratory Test Interactions .................................................................... 11
10 CLINICAL PHARMACOLOGY ....................................................................................... 11
10.1 Mechanism of Action.................................................................................. 11
10.2 Pharmacodynamics .................................................................................... 11
10.3 Pharmacokinetics ....................................................................................... 11
11 STORAGE, STABILITY AND DISPOSAL ......................................................................... 12
12 SPECIAL HANDLING INSTRUCTIONS........................................................................... 12
PART II: SCIENTIFIC INFORMATION ...................................................................................... 13
13 PHARMACEUTICAL INFORMATION............................................................................ 13
14 CLINICAL TRIALS........................................................................................................ 13
14.2 Study Results ............................................................................................. 13
15 MICROBIOLOGY ........................................................................................................ 15
16 NON-CLINICAL TOXICOLOGY ..................................................................................... 15
PATIENT MEDICATION INFORMATION ................................................................................. 16
PART I: HEALTH PROFESSIONAL INFORMATION
1 INDICATIONS
STROMECTOL® (ivermectin) is indicated for the treatment of:
- intestinal strongyloidiasis;
- onchocerciasis;
1.1 Pediatrics
Pediatrics (less than 15 kg): Safety and effectiveness of STROMECTOL® in pediatric patients weighing less than 15 kg has not been established (See 7. WARNINGS and PRECAUTIONS).
1.2 Geriatrics
Geriatrics (≥65 years of age): Evidence from clinical studies and experience in the geriatric population has not identified differences in responses between the elderly and younger patients. (See 7. WARNINGS and PRECAUTIONS).
2 CONTRAINDICATIONS
STROMECTOL® is contraindicated in patients who are hypersensitive to this drug or to any ingredient in the formulation, including any non-medicinal ingredient, or component of the container. For a complete listing, see 6. DOSAGE FORMS, STRENGTHS, COMPOSITION AND PACKAGING.
4 DOSAGE AND ADMINISTRATION
4.1 Dosing Considerations
The dosage tables below show the number of 3-mg tablets recommended for various body weights for each indication.
4.2 Recommended Dose and Dosage Adjustment
Strongyloidiasis (See Table 1)
The recommended dosage of STROMECTOL® for the treatment of strongyloidiasis is a single oral dose designed to provide approximately 200 mcg of ivermectin per kg of body weight. (See TABLE 1 for dosage guidelines.) Patients should take tablets on an empty stomach with water. In general, additional doses are not necessary. However, follow-up stool examinations should be performed to verify eradication of infection. (See 14. CLINICAL TRIALS)
| TABLE 1 | |
Dosage Guidelines for Strongyloidiasis Dosage by WEIGHT | |
| BODY WEIGHT (kg) | DOSE (approx. 200 mcg/kg) (Number of 3-mg tablets) |
| 15 to 24 | one |
| 25 to 35 | two |
| 36 to 50 | three |
| 51 to 65 | four |
| 66 to 79 | five |
| ≥80 | approx. 200 mcg/kg |
Onchocerciasis (See Table 2)
The recommended dosage of STROMECTOL® for the treatment of onchocerciasis is a single oral dose designed to provide approximately 150 mcg/kg of body weight. Patients should take tablets on an empty stomach with water. In mass distribution campaigns for onchocerciasis, the most commonly used dose interval is 12 months. For the treatment of individual patients, retreatment may be considered at intervals as short as 3 months.
| TABLE 2 | |
Dosage Guidelines for Onchocerciasis Dosage by WEIGHT | |
| For Onchocerciasis | |
| BODY WEIGHT (kg) | DOSE when given once every 12 months (approx. 150 mcg/kg) Number of 3-mg Tablets |
| 15 to 25 | one |
| 26 to 44 | two |
| 45 to 64 | three |
| 65 to 84 | four |
| ≥85 | approx. 150 mcg/kg |
4.4 Administration
STROMECTOL® is administered as a single oral dose given with water on an empty stomach.
4.5 Missed Dose
The dosing of STROMECTOL® for Onchocerciasis or Strongyloidiasis is a single oral dose (see 4. DOSAGE AND ADMINISTRATION).
5 OVERDOSAGE
It is important to adhere to recommended dosages. Cases of depressed level of consciousness and coma have been reported with overdosage of ivermectin. In accidental intoxication with or significant exposure to unknown quantities of veterinary formulations of ivermectin in humans, either by ingestion, inhalation, injection, or exposure to body surfaces, the following adverse effects have been reported most frequently: rash, contact dermatitis, edema, headache, dizziness, asthenia, nausea, vomiting, and diarrhea. Other adverse effects that have been reported include: seizure, ataxia, dyspnea, abdominal pain, paresthesia, and urticaria.
In case of accidental poisoning, supportive therapy, if indicated, should include parenteral fluids and electrolytes, respiratory support (oxygen and mechanical ventilation if necessary) and pressor agents if clinically significant hypotension is present. Induction of emesis and/or gastric lavage as soon as possible, followed by purgatives and other routine antipoison measures may be indicated if needed to prevent absorption of ingested material.
In a study in which healthy volunteers were orally administered up to 2000 mcg/kg ivermectin in a fasted state or up to 600 mcg/kg ivermectin following a high-fat (48.6 g of fat) meal, there were no indications of central nervous system toxicity observed at any dose irrespective of food intake. (See 9. DRUG INTERACTIONS)
| For management of a suspected drug overdose, contact your regional poison control centre. |
6 DOSAGE FORMS, STRENGTHS, COMPOSITION AND PACKAGING
Table 3 – Dosage Forms, Strengths, Composition and Packaging
STROMECTOL® tablets, 3 mg, are white, round, flat, bevel-edged tablets engraved with MSD on one side and 32 on the other side. They are supplied in unit dose packages in cartons of 4 tablets.
7 WARNINGS AND PRECAUTIONS
General
Do not use STROMECTOL ® if there is a history of hypersensitivity reaction to this product
Rarely, patients who are also heavily infected with Loa loa may develop a serious or even fatal
| Route of Administration | Dosage Form / Strength/Composition | Non-medicinal Ingredients |
| oral | tablet 3 mg | butylated hydroxyanisole, citric acid, magnesium stearate, microcrystalline cellulose and pregelatinized starch |
encephalopathy either spontaneously or following treatment with an effective microfilaricide. In these patients, the following adverse experiences have also been reported: pain (including neck and back pain), red eye, conjunctival hemorrhage, dyspnea, urinary and/or fecal incontinence, difficulty in standing/walking, mental status changes, confusion, lethargy, stupor, seizures, or coma. This syndrome has been seen very rarely following the use of STROMECTOL®. In individuals who warrant treatment with STROMECTOL® for any reason and have had significant exposure to Loa loa-endemic areas of West or Central Africa, pretreatment assessment for loiasis and careful post-treatment follow-up should be implemented.
Neurological toxicity, including depressed level of consciousness and coma, has also been reported in patients with the use of ivermectin in the absence of Loa loa infection. These events have generally resolved with supportive care and the discontinuation of ivermectin. (See 5. OVERDOSAGE)
After treatment with microfilaricidal drugs, patients with hyperreactive onchodermatitis (sowda) may be more likely than others to experience severe adverse reactions, especially edema and aggravation of onchodermatitis.
Onchocerciasis
STROMECTOL® has no activity against adult Onchocerca volvulus parasites. The adult parasites reside in subcutaneous nodules which are infrequently palpable. Surgical excision of these nodules (nodulectomy) may be considered in the management of patients with onchocerciasis, since this procedure will eliminate the microfilariae-producing adult parasites. Alternatively repeated follow-up and retreatment with STROMECTOL® may be required.
Historical data have shown that microfilaricidal drugs, such as diethylcarbamazine citrate (DEC), might cause cutaneous and/or systemic reactions of varying severity (the Mazzotti reaction) and ophthalmological reactions in patients with onchocerciasis. These reactions are probably due to allergic and inflammatory responses to the death of microfilariae. Patients treated with STROMECTOL® for onchocerciasis may experience these reactions in addition to clinical adverse reactions possibly, probably, or definitely related to the drug itself. (See 8. ADVERSE REACTIONS)
The treatment of severe Mazzotti reactions has not been subjected to controlled clinical trials. Oral hydration, recumbency, intravenous normal saline, and/or parenteral corticosteroids have been used to treat postural hypotension. Antihistamines and/or non-steroidal anti-inflammatory drugs such as aspirin/acetaminophen (paracetamol) have been used for most mild to moderate cases.
No data are available to support the use of STROMECTOL® prophylactically against onchocerciasis.
Strongyloidiasis In Immunocompromised Hosts
In immunocompromised (including HIV-infected) patients being treated for intestinal strongyloidiasis, repeated courses of therapy have been required. Adequate and well-controlled clinical studies have not been conducted in such patients to determine the optimal dosing regimen. Several treatments, e.g., at 2 week intervals, may be required, and even then cure may not be achievable. Control of extra-intestinal strongyloidiasis in these patients is difficult, and suppressive therapy, i.e., once per month may be helpful.
The patient should be reminded of the need for repeated stool examinations to document clearance of infection with Strongyloides stercoralis.
7.1 Special Populations
7.1.1 Pregnant Women
Safety in pregnant women has not been established. Limited post marketing surveillance has not established a relationship between exposure to ivermectin during the first trimester and the occurrence of adverse pregnancy outcomes. The frequencies of congenital anomalies, spontaneous abortions, fetal deaths/stillbirths and infant mortalities in approximately 400 women inadvertently treated with ivermectin during the first trimester in mass treatment campaigns for onchocerciasis were similar to frequencies in women not treated with ivermectin during pregnancy. There are not sufficient data to assess the safety of a single dose of ivermectin administered during the second and third trimesters.
Ivermectin caused cleft palates in mice and rats at oral doses of 0.4 and 10 mg/kg/day respectively, and cleft palates and clubbed feet in rabbits dosed at 3 mg/kg/day. These developmental effects were found only at or near doses that were maternotoxic to the pregnant female.
Treatment of pregnant women with ivermectin should be limited to mass treatment campaigns in which the risk of complications from untreated onchocerciasis exceeds the potential risk to the fetus from treatment.
7.1.2 Breast-feeding
Less than 2% of the administered dose of ivermectin appeared in breast milk. Safety in newborn infants has not been established; therefore, the drug should be given to nursing mothers only if the benefit to the mother outweighs the potential risk to the breast-fed infant, and treatment of mothers who intend to breast feed their infants should be delayed until at least 1 week after birth of the child.
7.1.3 Pediatrics
Pediatrics (less than 15 kg): The safety and efficacy of STROMECTOL® in pediatric patients weighing less than 15 kg has not been established
7.1.4 Geriatrics
Clinical studies of STROMECTOL® did not include sufficient numbers of subjects aged 65 and over to determine whether they respond differently from younger subjects. Other reported clinical experience has not identified differences in responses between the elderly and younger patients. In general, treatment of an elderly patient should be cautious, reflecting the greater frequency of decreased hepatic, renal, or cardiac function, and of concomitant disease or other drug therapy.
8 ADVERSE REACTIONS
8.1 Adverse Reaction Overview
STROMECTOL® (ivermectin) has been demonstrated to be generally well tolerated. For the most part side effects have been mild and transient in nature.
8.2 Clinical Trial Adverse Reactions
Clinical trials are conducted under very specific conditions. The adverse reaction rates observed in the clinical trials; therefore, may not reflect the rates observed in practice and should not be compared to the rates in the clinical trials of another drug. Adverse reaction information from clinical trials may be useful in identifying and approximating rates of adverse drug reactions in real-world use.
Strongyloidiasis
In four clinical studies involving a total of 109 patients given either one or two doses of 170 to 200 mcg/kg of ivermectin, the following adverse reactions were reported as possibly, probably, or definitely related to ivermectin:
Body as a whole: asthenia/fatigue (0.9%), abdominal pain (0.9%)
Gastrointestinal: anorexia (0.9%), constipation (0.9%), diarrhea (1.8%), nausea (1.8%), vomiting (0.9%)
Nervous System/Psychiatric: dizziness (2.8%), somnolence (0.9%), vertigo (0.9%), tremor (0.9%)
Skin: pruritus (2.8%), rash (0.9%), and urticaria (0.9%)
In comparative trials, patients treated with STROMECTOL® experienced more abdominal distention and chest discomfort than patients treated with albendazole. However, STROMECTOL® was better tolerated than thiabendazole in comparative studies involving 37 patients treated with thiabendazole.
The Mazzotti-type and ophthalmologic reactions associated with the treatment of onchocerciasis or the disease itself would not be expected to occur in strongyloidiasis patients treated with ivermectin.
Onchocerciasis
In clinical trials involving 963 adult patients treated with 100 to 200 mcg/kg ivermectin, worsening of the following signs and symptoms during the first 4 days post-treatment were reported: arthralgia/synovitis (9.3%), axillary lymph node enlargement and tenderness (11.0% and 4.4%, respectively), cervical lymph node enlargement and tenderness (5.3% and 1.2%, respectively), inguinal lymph node enlargement and tenderness (12.6% and 13.9%, respectively), other lymph node enlargement and tenderness (3.0% and 1.9%, respectively), pruritus (27.5%), skin involvement including edema, papular and pustular or frank urticarial rash (22.7%), and fever (22.6%). These signs and symptoms are considered part of the Mazzotti-type reactions. (See 7. WARNINGS and PRECAUTIONS).
In clinical trials, ophthalmological conditions were examined in 963 adult patients before treatment, at day 3, and months 3 and 6 after treatment with 100 to 200 mcg/kg ivermectin. Changes observed were primarily deterioration from baseline 3 days post-treatment. Most changes either returned to baseline condition or improved over baseline severity at the month 3 and 6 visits. The percentages of patients with worsening of the following conditions at day 3, month 3 and 6, respectively, were: limbitis: 5.5%, 4.8%, and 3.5% and punctate opacity: 1.8%, 1.8%, and 1.4%. The corresponding percentages for patients treated with placebo were: limbitis: 6.2%, 9.9% and 9.4% and punctate opacity: 2.0%, 6.4% and 7.2%.
In clinical trials involving 963 adult patients who received 100 to 200 mcg/kg ivermectin, the following clinical adverse reactions were reported as possibly, probably, or definitely related to the drug in ≥1% of the patients: facial edema (1.2%), peripheral edema (3.2%), orthostatic hypotension (1.1%), and tachycardia (3.5%). Drug-related headache and myalgia occurred in <1% of patients (0.2%, and 0.4%, respectively). However, these were the most common adverse experiences reported overall during these trials regardless of causality (22.3% and 19.7%, respectively).
A similar safety profile was observed in an open study in pediatric patients ages 6 to 13.
The following ophthalmological side effects do occur due to the disease itself but have also been reported after treatment with ivermectin: abnormal sensation in the eyes, eyelid edema, anterior uveitis, conjunctivitis, limbitis, keratitis, and chorioretinitis or choroiditis. These have rarely been severe or associated with loss of vision and have generally resolved without corticosteroid treatment.
8.4 Abnormal Laboratory Findings: Hematologic, Clinical Chemistry and Other Quantitative Data
Clinical Trial Findings
Strongyloidiasis
In clinical trials involving 109 patients given either one or two doses of 170 to 200 mcg/kg ivermectin, the laboratory adverse experiences, reported irrespective of drug relationship, were leukopenia/anemia in one patient and elevated ALT/alkaline phosphatase in one patient.
Onchocerciasis
In controlled clinical trials, the following laboratory adverse experiences were reported as possibly, probably, or definitely related to the drug in ≥1% of the patients: eosinophilia (3%) and hemoglobin increase (1%).
8.5 Post-Market Adverse Reactions
Onchocerciasis
Conjunctival Haemorrhage
All indications
Hypotension (mainly orthostatic hypotension), worsening of bronchial asthma, toxic epidermal necrolysis, Stevens-Johnson syndrome, seizures, hepatitis, elevation of liver enzymes, and elevation of bilirubin.
Neurological toxicity including depressed level of consciousness and coma (See 7. WARNINGS AND PRECAUTIONS).
9 DRUG INTERACTIONS
9.2 Drug Interactions Overview
Post-marketing reports of increased INR (International Normalized Ratio) have been reported when STROMECTOL® was co-administered with warfarin.
9.4 Drug-Drug Interactions
In vitro studies using human liver microsomes and recombinant CYP450 enzymes have shown that ivermectin is primarily metabolized by CYP3A4. Depending on the in vitro method used, CYP2D6 and CYP2E1 were also shown to be involved in the metabolism of ivermectin but to a significantly lower extent compared to CYP3A4. The findings of in vitro studies using human liver microsomes suggest that clinically relevant concentrations of ivermectin do not significantly inhibit the metabolizing activities of CYP3A4, CYP2D6, CYP2C9, CYP1A2, and CYP2E1.
9.5 Drug-Food Interactions
A multiple-dose clinical safety study has been conducted to assess the safety and pharmacokinetic properties of STROMECTOL® in healthy volunteers. Subjects received oral doses of 30 to 120 mg STROMECTOL® in a fasted state or 30 mg STROMECTOL® following a standard high-fat (48.6 g of fat) meal. Administration of 30 mg STROMECTOL® following a high-fat meal resulted in an approximate 2.5-fold increase in bioavailability relative to administration of 30 mg STROMECTOL® in the fasted state. However, there were no indications of central nervous system toxicity associated with either regimen. (See 5. OVERDOSAGE)
9.6 Drug-Herb Interactions
Interactions with herbal products has not been established
9.7 Drug-Laboratory Test Interactions
Interactions with laboratory test has not been established
10 CLINICAL PHARMACOLOGY
10.1 Mechanism of Action
Ivermectin is a member of the avermectin class of broad-spectrum antiparasitic agents which have a unique mode of action. Compounds of the class bind selectively and with high affinity to glutamate-gated chloride ion channels which occur in invertebrate nerve and muscle cells. This leads to an increase in the permeability of the cell membrane to chloride ions with hyperpolarization of the nerve or muscle cell, resulting in paralysis and death of the parasite. Compounds of this class may also interact with other ligand-gated chloride channels, such as those gated by the neurotransmitter gamma-aminobutyric acid (GABA).
10.2 Pharmacodynamics
STROMECTOL®, an anthelmintic, is derived from the avermectins, a class of highly active broad-spectrum antiparasitic agents isolated from fermentation broths of Streptomyces avermitilis
10.3 Pharmacokinetics
Following oral administration of ivermectin, plasma concentrations are approximately proportional to the dose. In two studies, after single 12-mg doses of STROMECTOL® in fasting healthy volunteers (representing a mean dose of 165 mcg/kg), the mean peak plasma concentrations of the major component (H2B1a) were 46.6 (±21.9) (range: 16.4-101.1) and 30.6 (±15.6) (range: 13.9-68.4) ng/mL, respectively, at approximately 4 hours after dosing. Ivermectin is metabolized in the liver, and ivermectin and/or its metabolites are excreted almost exclusively in the feces over an estimated 12 days, with less than 1% of the administered dose excreted in the urine. The plasma half-life of ivermectin in man is approximately 18 hours following oral administration.
The safety and pharmacokinetic properties of ivermectin were further assessed in a multiple-dose clinical pharmacokinetic study involving healthy volunteers. Subjects received oral doses of 30 to
120 mg (333 to 2000 mcg/kg) ivermectin in a fasted state or 30 mg (333 to 600 mcg/kg) ivermectin following a standard high-fat (48.6 g of fat) meal. Administration of 30 mg ivermectin following a high-fat meal resulted in an approximate 2.5-fold increase in bioavailability relative to administration of 30 mg ivermectin in the fasted state.
In vitro studies using human liver microsomes and recombinant CYP450 enzymes have shown that ivermectin is primarily metabolized by CYP3A4. Depending on the in vitro method used, CYP2D6 and CYP2E1 were also shown to be involved in the metabolism of ivermectin but to a significantly lower extent compared to CYP3A4. The findings of in vitro studies using human liver microsomes suggest that clinically relevant concentrations of ivermectin do not significantly inhibit the metabolizing activities of CYP3A4, CYP2D6, CYP2C9, CYP1A2, and CYP2E1.
Special Populations and Conditions
The pharmacokinetics of STROMECTOL® has not been studied in patients with impaired hepatic or renal function.
11 STORAGE, STABILITY AND DISPOSAL
Store at 15-30°C.
12 SPECIAL HANDLING INSTRUCTIONS
Not applicable
PART II: SCIENTIFIC INFORMATION
13 PHARMACEUTICAL INFORMATION
Drug Substance
Proper name: Ivermectin
Chemical name: Ivermectin is a mixture which contains not less than 95.0 percent and not more than 102.0 percent for the sum of component 5-O-demethyl-22,23-dihydroavermectin A1a (H2B1a) plus component 5-O-demethyl-25-de(1-methylpropyl)-25-(1-methylethyl)-22,23-dihydroavermectin A1a (H2B1b), calculated on the anhydrous and alcohol- and formamide- free basis; and the ratio (calculated by area percentage) of component H2Ba / H2B1a + H2B1b) is not less than 90.0 percent
Molecular formula and molecular mass: H2B1a: C48H74O14; 875.1
H2B1b: C47H72O14; 861.1
Structural formula:
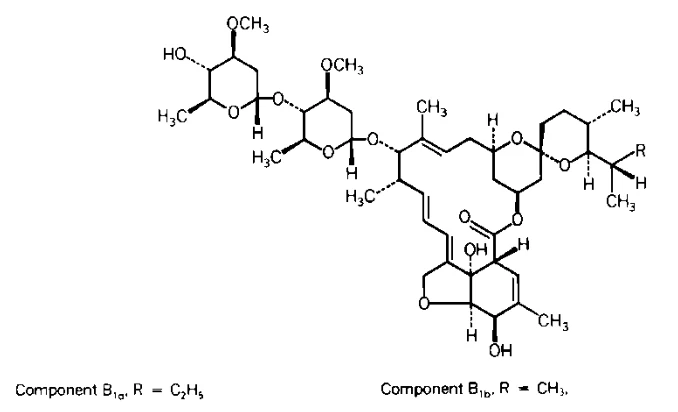
Physicochemical properties: Ivermectin is a white to yellowish-white, crystalline powder which is practically insoluble in water, freely soluble in methanol and soluble in 95% ethanol and acetone.
14 CLINICAL TRIALS
14.2 Study Results
Onchocerciasis
The evaluation of ivermectin in the treatment of onchocerciasis is based on the results of clinical studies involving 1278 patients. In a double-blind, placebo-controlled study involving adult patients with moderate to severe onchocercal infection, patients who received a single dose of 150 mcg/kg ivermectin experienced an 83.2% and 99.5% decrease in skin microfilariae count (geometric mean) 3 days and 3 months after the dose, respectively. A marked reduction of >90% was maintained for up to 12 months after the single dose. As with other microfilaricidal drugs, there was an increase in the microfilariae count in the anterior chamber of the eye at day 3 after treatment in some patients. However, at 3 and 6 months after the dose, a significantly greater percentage of patients treated with ivermectin had decreases in microfilariae count in the anterior chamber than patients treated with placebo.
In a separate open study involving pediatric patients ages 6 to 13 (n=103; weight range: 17 to 41 kg), similar decreases in skin microfilariae counts were observed for up to 12 months after dosing.
Strongyloidiasis
Efficacy and safety for the use of ivermectin in the treatment of strongyloidiasis have been studied in two controlled clinical studies using albendazole as the comparative agent, and three controlled studies using thiabendazole as the comparative agent. Efficacy, as measured by cure rate, was defined as the absence of larvae in follow-up stool examinations. Based on this criterion, efficacy was significantly greater for ivermectin (a single dose of 170 to 200 mcg/kg) than for albendazole (200 mg b.i.d. for 3 days). Ivermectin administered as a single dose of 200 mcg/kg for 1 day was as efficacious as thiabendazole administered at 25 mg/kg b.i.d. for 3 days.
Table 4: Summary of Cure Rates for Ivermectin Versus Comparative Agents in the Treatment of Strongyloidiasis
| |||||
| Comparative Agent | ||||
| Albendazole* Comparative International Study WHO Study |
|
| |||
|
|
| |||
* 200 mg b.i.d. for 3 days ** 25 mg/kg b.i.d. for 3 days | |||||
In one study conducted in France, a non-endemic area where there was no possibility of reinfection, several patients were observed to have recrudescence of Strongyloides larvae in their stool as long as 106 days following ivermectin therapy. Therefore, at least three stool examinations should be conducted over the three months following treatment to ensure eradication. If recrudescence of larvae is observed, retreatment with ivermectin is indicated. Concentration techniques (such as using a Baermann apparatus) should be employed when performing these stool examinations, as the number of Strongyloides larvae per gram of feces may be very low.
15 MICROBIOLOGY
Ivermectin is a member of the avermectin class of broad-spectrum antiparasitic agents which have a unique mode of action. Compounds of the class bind selectively and with high affinity to glutamate-gated chloride ion channels which occur in invertebrate nerve and muscle cells. This leads to an increase in the permeability of the cell membrane to chloride ions with hyperpolarization of the nerve or muscle cell, resulting in paralysis and death of the parasite. Compounds of this class may also interact with other ligand-gated chloride channels, such as those gated by the neurotransmitter gamma-aminobutyric acid (GABA).
The selective activity of compounds of this class is attributable to the facts that some mammals do not have glutamate-gated chloride channels and that the avermectins have a low affinity for mammalian ligand-gated chloride channels. In addition, ivermectin does not readily cross the blood-brain barrier in humans.
Ivermectin is active against various life-cycle stages of many but not all nematodes. It is active against the tissue microfilariae of Onchocerca volvulus but not against the adult form. Its activity against Strongyloides stercoralis is limited to the intestinal stages.
16 NON-CLINICAL TOXICOLOGY
General Toxicology: Acute oral studies with ivermectin in mice, rats, and monkeys have shown clear species and strain differences in sensitivity, with rodents being relatively sensitive to the CNS toxicity produced by the compound. Doses of 200 mcg/kg in mice and slightly higher doses in rats have produced tremors and ataxia, while a 200 mcg/kg dose was generally well tolerated in studies in a variety of species. Acute oral studies in rhesus monkeys demonstrated that the minimum toxic dose was 2,000 mcg/kg or approximately 10-fold the clinical dose. Doses up to 24 mg/kg in this species (120-fold the clinical dose) produced only slight increases in the observed toxic effects including emesis, mydriasis, and sedation. A repeated dose study of 2 weeks' duration in rhesus monkeys produced no adverse effects at doses up to 1,200 mcg/kg/day. Fourteen-week studies in rats and dogs indicated no adverse effects at doses of 400 and 500 mcg/kg/day, respectively.
Significant lethality was observed in mice and rats after single oral doses of 25 to 50 mg/kg and 40 to 50 mg/kg, respectively. No significant lethality was observed in dogs after single oral doses of up to 10 mg/kg. At these doses, the treatment related signs that were observed in these animals include ataxia, bradypnea, tremors, ptosis, decreased activity, emesis, and mydriasis.
Carcinogenicity: Long-term studies have not been performed to evaluate the carcinogenic potential of ivermectin.
Genotoxicity: Ivermectin is negative in the Ames microbiological mutation and the mouse lymphoma mutation assays; it did not induce unscheduled DNA synthesis in human fibroblast cell culture.
Reproductive and Developmental Toxicology: Breeding performance in various species has not been adversely affected by ivermectin.
Ivermectin caused cleft palates in mice and rats at oral doses of 0.4 and 10 mg/kg/day respectively, and cleft palates and clubbed feet in rabbits dosed at 3 mg/kg/day. These development effects were found only at or near doses that were maternotoxic to the pregnant female.