


Product Monograph - Succinylcholine Chloride Injection USP
ACTION AND CLINICAL PHARMACOLOGY
Succinylcholine is an ultra short-acting, depolarizing-type, skeletal muscle relaxant. As does acetylcholine, it combines with the cholinergic receptors of the motor end plate to produce depolarization. This depolarization may be observed as fasciculations. Subsequent neuromuscular transmission is inhibited so long as adequate concentration of succinylcholine remains at the receptor site. Onset of flaccid paralysis is rapid (less than one minute after i.v. administration), and with single administration lasts approximately 4 to 6 minutes.
Succinylcholine is rapidly hydrolysed by plasma cholinesterase to succinylmonocholine (which possesses clinically insignificant depolarizing muscle relaxant properties) and then more slowly to succinic acid and choline (see PRECAUTIONS). About 10% of the drug is excreted unchanged in the urine. The paralysis following administration of succinylcholine chloride is progressive, initially involving consecutively the levator muscles of the face, muscles of the glottis and finally the intercostals and the diaphragm and all other skeletal muscles.
Succinylcholine has no direct action on the uterus or other smooth muscle structures. Because it is highly ionized and has low fat solubility, it does not readily cross the placenta.
Tachyphylaxis occurs with repeated administration (see PRECAUTIONS).
Depending on the dose and duration of succinylcholine administration, the characteristic depolarizing neuromuscular block (Phase I block) may change to a block with characteristics superficially resembling a nondepolarizing block (Phase II block). This may be associated with prolonged respiratory muscle paralysis or weakness in patients who manifest the transition to Phase II block. When this diagnosis is confirmed by peripheral nerve stimulation, it may sometimes be reversed with anticholinesterase drugs such as neostigmine (see PRECAUTIONS). Anticholinesterase drugs may not always be effective. If given before succinylcholine is metabolized by cholinesterase, anticholinesterase drugs may prolong rather than shorten paralysis.
Succinylcholine has no direct effect on the myocardium. Succinylcholine stimulates both autonomic ganglia and muscarinic receptors which may cause changes in cardiac rhythm, predominantly bradycardia and occasional asystoles. Changes in rhythm including cardiac arrest, may also result from vagal stimulation, which may occur during surgical procedures, or from hyperkalemia, particularly in children (see PRECAUTIONS-Pediatric Use). These effects are enhanced by halogenated anesthetics.
Succinylcholine causes an increase in intraocular pressure immediately after its injection and during the fasciculation phase, and causes slight increases which may persist after onset of complete paralysis (see WARNINGS).
Succinylcholine may cause slight increases in intracranial pressure immediately after its injection and during the fasciculation phase (see PRECAUTIONS).
As with other neuromuscular blocking agents, the potential for releasing histamine is present following succinylcholine administration. Signs and symptoms of histamine-mediated release such as flushing, hypotension and bronchoconstriction are, however, uncommon in normal clinical usage.
Succinylcholine has no effect on consciousness, pain threshold or cerebration. It should be used only with adequate anesthesia (see WARNINGS).
The onset and duration of action of succinylcholine may be altered by dehydration and electrolyte imbalance, and by the use of other medications such as depolarizing or non-depolarizing muscle relaxants.
Pharmacogenomics: The RYR1 and CACNA1S are polymorphic genes and multiple pathogenic variants have been associated with Malignant Hyperthermia Susceptibility (MHS) in patients receiving succinylcholine,. Case reports as well as ex vivo studies have identified multiple variants in RYR1 and CACNA1S associated with MHS. Variant pathogenicity should be assessed based on prior clinical experience, functional studies, prevalence information, or other relevant evidence (see CONTRAINDICATIONS, WARNINGS).
INDICATIONS AND CLINICAL USE
Succinylcholine chloride is indicated as an adjunct to general anesthesia, to facilitate tracheal intubation, and to provide skeletal muscle relaxation during surgery or mechanical ventilation.
CONTRAINDICATIONS
Succinylcholine is contraindicated in persons with known or suspected genetic susceptibility to malignant hyperthermia, skeletal muscle myopathies, and known hypersensitivity to the drug.
It is also contraindicated in patients after the acute phase of injury following major burns, multiple trauma, extensive denervation of skeletal muscle, or upper motor neuron injury, unless clinical circumstances require immediate securing of the airway, because succinylcholine administered to such individuals may result in severe hyperkalemia which may result in cardiac arrest (see WARNINGS). The risk of hyperkalemia in these patients increases over time and usually peaks at 7 to 10 days after the injury. The risk is dependent on the extent and location of the injury. The precise time of onset and the duration of the risk period are not known.
Acute rhabdomyolysis with hyperkalemia can occur when used in individuals with a skeletal muscle myopathy such as Duchenne's muscular dystrophy (see PRECAUTIONS – Pediatric Use).
WARNINGS
WARNING: VENTRICULAR DYSRHYTHMIAS, CARDIAC ARREST, AND DEATH FROM HYPERKALEMIC RHABDOMYOLYSIS IN PEDIATRIC PATIENTS
|
|---|
Succinylcholine should be used only by those skilled in the management of artificial respiration and only when facilities are instantly available for tracheal intubation and for providing adequate ventilation of the patient, including the administration of oxygen under positive pressure and the elimination of carbon dioxide. The clinician must be prepared to assist or control respiration.
To avoid distress to the patient, succinylcholine should not be administered before unconsciousness has been induced. In emergency situations, however it may be necessary to administer succinylcholine before unconsciousness is induced.
Succinylcholine is metabolized by plasma cholinesterase and should be used with caution, if at all, in patients known to be or suspected of being homozygous for the atypical plasma cholinesterase gene.
Hyperkalemia
Succinylcholine should be administered with GREAT CAUTION to patients suffering from hyperkalemia because in these circumstances succinylcholine may induce serious cardiac arrhythmias or cardiac arrest due to hyperkalemia.
GREAT CAUTION should be observed if succinylcholine is administered to patients during the acute phase of injury following major burns, multiple trauma, extensive denervation of skeletal muscle, or upper motor neuron injury (see CONTRAINDICATIONS). The risk of hyperkalemia in these patients increases over time and usually peaks at 7 to 10 days after the injury. The risk is dependent on the extent and location of the injury. The precise time of onset and the duration of the risk period are undetermined. Patients with chronic abdominal infection, subarachnoid hemorrhage, or conditions causing degeneration of central and peripheral nervous systems should receive succinylcholine with GREAT CAUTION because of the potential for developing severe hyperkalemia.
Immediate treatment of hyperkalemia should include hyperventilation, i.v. calcium, i.v. sodium bicarbonate and I.V. glucose (with or without insulin).
Malignant Hyperthermia
Succinylcholine may trigger malignant hyperthermia, a skeletal muscle hypermetabolic state leading to high oxygen demand. Fatal outcomes of malignant hyperthermia have been reported.
The risk of developing malignant hyperthermia increases with the concomitant administration of succinylcholine and volatile anesthetic agents.
Succinylcholine Chloride Injection USP can induce malignant hyperthermia in patients with known or suspected susceptibility based on genetic factors or family history, including those with certain inherited ryanodine receptor (RYR1) or dihydropyridine receptor (CACNA1S) variants (see CONTRAINDICATIONS).
Signs consistent with malignant hyperthermia may include hyperthermia, hypoxia, hypercapnia, muscle rigidity (e.g., jaw muscle spasm), tachycardia (e.g., particularly that unresponsive to deepening anesthesia or analgesic medication administration), tachypnea, cyanosis, arrhythmias, hypovolemia, and hemodynamic instability. Skin mottling, coagulopathies, and renal failure may occur later in the course of the hypermetabolic process.
Successful treatment of malignant hyperthermia depends on early recognition of the initial clinical signs such as jaw muscle spasm, increase of end-tidal carbon dioxide concentrations, generalized rigidity to initial administration of succinylcholine for tracheal intubation, or failure of tachycardia to respond to deepening anesthesia. If malignant hyperthermia is suspected, discontinue all triggering agents (i.e., volatile anesthetic agents and succinylcholine), administer intravenous dantrolene sodium, and initiate supportive therapies. Consult prescribing information for intravenous dantrolene sodium for additional information on patient management. Supportive therapies include administration of supplemental oxygen and respiratory support based on clinical need, maintenance of hemodynamic stability and adequate urinary output, management of fluid and electrolyte balance, correction of acid base derangements, and institution of measures to control rising temperature.
Other
In adults the incidence of bradycardia, which may progress to asystole, is greater after a second dose of succinylcholine. In infants and young children, bradycardia and transient asystole may occur after one dose of succinylcholine. The incidence and severity of bradycardia is greater in infants and children than in adults. Pretreatment with anticholinergic agents (e.g. atropine), in most cases, will reduce the occurrence of bradyarrhythmias.
Succinylcholine causes an increase in intraocular pressure. It should not be used in instances in which an increase in intraocular pressure is undesirable (e.g. narrow angle glaucoma, penetrating eye injury) unless the potential benefit of this use outweighs the potential risk.
Succinylcholine is acidic (pH = 3.5) and should not be mixed with alkaline solutions having a pH greater than 8.5 (e.g. barbiturate solutions) (see PHARMACEUTICAL INFORMATION, Stability - Compatibility).
PRECAUTIONS
General
When succinylcholine is given over a prolonged period of time, the characteristic depolarization block of the myoneural junction (Phase I block) may change to a block with characteristics superficially resembling a nondepolarizing block (Phase II block). Prolonged respiratory muscle paralysis or weakness may be observed in patients manifesting this transition to Phase II block.
The transition from Phase I to Phase II block has been reported in 7 of 7 patients studied under halothane anesthesia after an accumulated dose of 2 to 4 mg/kg succinylcholine (administered in repeated, divided doses). The onset of Phase II block coincided with the onset of tachyphylaxis and prolongation of spontaneous recovery. In another study, using balanced anesthesia (N2O/O2/narcotic-thiopental) and succinylcholine infusion, the transition was less abrupt, with great individual variability in the dose of succinylcholine required to produce Phase II block. Of 32 patients studied, 24 developed Phase II block. Tachyphylaxis was not associated with the transition to Phase II block, and 50% of the patients who developed Phase II block experienced prolonged recovery.
When Phase II block is suspected in cases of prolonged neuromuscular blockade, positive diagnosis should be made by peripheral nerve stimulation, prior to administration of any anticholinesterase drug. Reversal of Phase II block is a medical decision which must be made upon the basis of the individual clinical pharmacology and the experience and judgment of the physician. The presence of Phase II block is indicated by fade of responses to successive stimuli (preferably "train of four"). The use of an anticholinesterase drug to reverse Phase II block should be accompanied by appropriate doses of an anticholinergic drug to prevent disturbances of cardiac rhythm. After adequate reversal of Phase II block with an anticholinesterase agent, the patient should be continually observed for at least 1 hour for signs of return of muscle relaxation. Reversal should not be attempted unless: (1) a peripheral nerve stimulator is used to determine the presence of Phase II block (since anticholinesterase agents will potentiate succinylcholine-induced Phase I block), and (2) spontaneous recovery of muscle twitch has been observed for at least 20 minutes and has reached a plateau with further recovery proceeding slowly; this delay is to ensure complete hydrolysis of succinylcholine by plasma cholinesterase prior to administration of the anticholinesterase agent. Should the type of block be misdiagnosed, depolarization of the type initially induced by succinylcholine (i.e. Phase I block), will be prolonged by an anticholinesterase agent.
Succinylcholine should be employed with caution in patients with fractures or muscle spasm because the initial muscle fasciculations may cause additional trauma.
Succinylcholine may cause a transient increase in intracranial pressure; however, adequate anesthetic induction prior to administration of succinylcholine will minimize this effect.
Succinylcholine may increase intragastric pressure, which could result in regurgitation and possible aspiration of stomach contents.
Neuromuscular blockade may be prolonged in patients with hypokalemia or hypocalcemia.
The action of succinylcholine may be altered by some carcinomas or renal disease.
Reduced Plasma Cholinesterase Activity
Succinylcholine should be used carefully in patients with reduced plasma cholinesterase (pseudocholinesterase) activity. The likelihood of prolonged neuromuscular block following administration of succinylcholine must be considered in such patients (see DOSAGE AND ADMINISTRATION).
Plasma cholinesterase activity may be diminished in the presence of genetic abnormalities of plasma cholinesterase (e.g. patients heterozygous or homozygous for atypical plasma cholinesterase gene), pregnancy, severe liver or kidney disease, malignant tumors, infections, burns, anemia, decompensated heart disease, peptic ulcer, or myxedema. Plasma cholinesterase activity may also be diminished by chronic administration of oral contraceptives, glucocorticoids, or certain monoamine oxidase inhibitors and by irreversible inhibitors of plasma cholinesterase, (e.g. organophosphate insecticides, echothiophate, and certain antineoplastic drugs).
Patients homozygous for atypical plasma cholinesterase gene (1 in 2500 patients) are extremely sensitive to the neuromuscular blocking effect of succinylcholine. In these patients, a 5 to 10 mg test dose of succinylcholine may be administered, or neuromuscular blockade may be produced by the cautious administration of a 1 mg/mL solution of succinylcholine by intravenous drip. Apnea or prolonged muscle paralysis should be treated with controlled respiration.
Drug Interactions
Drugs which may enhance the neuromuscular blocking action of succinylcholine include: promazine, oxytocin, aprotinin, certain non-penicillin antibiotics, quinidine, β-adrenergic blockers, procainamide, lidocaine, trimethaphan, lithium carbonate, magnesium salts, quinine, chloroquine, diethylether, isoflurane, desflurane, metoclopramide and terbutaline. The presence of an inhalational anesthetic may exacerbate the side effects of succinylcholine in infants and children (see ADVERSE REACTIONS).
The neuromuscular blocking effect of succinylcholine may be enhanced by drugs that reduce plasma cholinesterase activity (e.g. chronically administered oral contraceptives, glucocorticoids, or certain monoamine oxidase inhibitors) or by drugs that irreversibly inhibit plasma cholinesterase (see PRECAUTIONS).
Drugs which either inhibit plasma pseudocholinesterase (such as neostigmine) or compete with succinylcholine for the enzyme (as does intravenous procaine) should not be given concurrently with succinylcholine.
If other neuromuscular blocking agents are to be used during the same procedure, the possibility of a synergistic or antagonistic effect should be considered.
Carcinogenesis, Mutagenesis, Impairment of Fertility
There have been no long-term studies performed in animals to evaluate carcinogenic potential.
Pregnancy
Teratogenic Effects
Animal reproduction studies have not been conducted with succinylcholine chloride. It is also not known whether succinylcholine can cause fetal harm when administered to a pregnant woman or can affect reproduction capacity. Succinylcholine should be given to a pregnant woman only if clearly needed.
Nonteratogenic Effects
Plasma cholinesterase levels are decreased by approximately 24% during pregnancy and for several days postpartum. Therefore, a higher proportion of patients may be expected to show increased sensitivity (prolonged apnea) to succinylcholine when pregnant than when nonpregnant.
Labor and Delivery
Succinylcholine is commonly used to provide muscle relaxation during delivery by cesarean section. While small amounts of succinylcholine are known to cross the placental barrier, under normal conditions the quantity of drug that enters fetal circulation after a single dose of 1 mg/kg to the mother should not endanger the fetus. However, since the amount of drug that crosses the placental barrier is dependent on the concentration gradient between the maternal and fetal circulations, residual neuromuscular blockade (apnea and flaccidity) may occur in the newborn after repeated high doses to, or in the presence of atypical plasma cholinesterase in, the mother.
Nursing Mothers
It is not known whether succinylcholine is excreted in human milk. Because many drugs are excreted in human milk, caution should be exercised following succinylcholine administration to a nursing woman.
Pediatric Use
There are rare reports of ventricular dysrhythmias, cardiac arrest and death secondary to acute rhabdomyolysis with hyperkalemia in apparently healthy infants and children who receive succinylcholine (see WARNINGS). Several of these individuals were subsequently found to be suffering from a myopathy such as Duchenne's muscular dystrophy whose clinical signs were not obvious. When a healthy appearing infant or child suddenly develops cardiac arrest soon after administration of succinylcholine, immediate treatment of hyperkalemia should include hyperventilation, i.v. calcium, i.v. sodium bicarbonate and i.v. glucose (with or without insulin). Treatment for acute rhabdomyolysis, including a single dose of dantrolene, should also be considered.
Unlike in adults, the incidence of bradycardia in infants and young children is common after one dose of succinylcholine. The incidence and severity of bradycardia is greater in infants and children than in adults. Pre-treatment with anticholinergic agents (e.g. atropine), in most cases, will reduce the occurrence of bradyarrhythmias.
ADVERSE REACTIONS
Adverse reactions to succinylcholine consist primarily of an extension of its pharmacological actions. Succinylcholine causes profound muscle relaxation resulting in respiratory depression to the point of apnea; this effect may be prolonged. Hypersensitivity reactions, including anaphylaxis may occur in rare instances. The following additional adverse reactions have been reported: cardiac arrest, malignant hyperthermia, arrhythmias, bradycardia, tachycardia, hypertension, hypotension, hyperkalemia, prolonged respiratory depression or apnea, increased intraocular pressure, muscle fasciculation, jaw rigidity, postoperative muscle pain, rhabdomyolysis with possible myoglobinuric acute renal failure, excessive salivation, and rash.
Reporting Side Effects You can report any suspected side effects associated with the use of health products to Health Canada by:
NOTE: Contact your health professional if you need information about how to manage your side effects. The Canada Vigilance Program does not provide medical advice. |
SYMPTOMS AND TREATMENT OF OVERDOSAGE
Symptoms
Overdosage with succinylcholine may result in neuromuscular block beyond the time needed for surgery and anesthesia. This may be manifested by skeletal muscle weakness, decreased respiratory reserve, low tidal volume, prolonged respiratory depression or apnea.
Treatment
The primary treatment is maintenance of a patent airway and respiratory support until recovery of normal respiration is assured. Depending on the dose and duration of succinylcholine administration, the characteristic depolarizing neuromuscular block (Phase I) may change to a block with characteristics superficially resembling a nondepolarizing block (Phase II) (see
PRECAUTIONS).
The decision to use neostigmine to reverse a Phase II succinylcholine-induced block depends on the judgment of the clinician in the individual case. Valuable information in regard to this decision will be gained by monitoring neuromuscular function. If neostigmine is used, its administration should be accompanied by appropriate doses of an anticholinergic agent such as atropine.
| For management of a suspected drug overdose, contact your regional poison control centre. |
|---|
DOSAGE AND ADMINISTRATION
The dosage of succinylcholine should be individualized and should always be determined by the clinician after careful assessment of the patient (see WARNINGS).
Parenteral drug products should be inspected visually for particulate matter and discoloration prior to administration whenever solution and container permit. Solutions which are not clear and colourless should not be used.
Adults
For Short Surgical Procedures
The average dose required to produce neuromuscular blockade and to facilitate tracheal intubation is 0.6 mg/kg Succinylcholine Chloride Injection USP given intravenously. The optimum dose will vary among individuals and may be from 0.3 to 1.1 mg/kg for adults.
Following administration of doses in this range, neuromuscular blockade develops in about 1 minute; maximum blockade may persist for about 2 minutes, after which recovery takes place within 4 to 6 minutes. However, very large doses may result in more prolonged blockade. A 5 to
10 mg test dose may be used to determine the sensitivity of the patient and the individual recovery time (see PRECAUTIONS).
For Long Surgical Procedures
The dose of succinylcholine administered by infusion depends upon the duration of the surgical procedure and the need for muscle relaxation. The average rate for an adult ranges between 2.5 and 4.3 mg per minute.
Solutions containing from 1 to 2 mg per mL succinylcholine have commonly been used for continuous infusion (see PHARMACEUTICAL INFORMATION, Stability-Compatibility). The more dilute solution (1 mg per mL) is probably preferable from the standpoint of ease of control of the rate of administration of the drug and, hence, of relaxation. This intravenous solution containing 1 mg per mL may be administered at a rate of 0.5 mg (0.5 mL) to 10 mg (10 mL) per minute to obtain the required amount of relaxation. The amount required per minute will depend upon the individual response as well as the degree of relaxation required. Avoid overburdening the circulation with a large volume of fluid. It is recommended that neuromuscular function be carefully monitored with a peripheral nerve stimulator when using succinylcholine by infusion in order to avoid overdose, detect development of Phase II block, follow its rate of recovery, and assess the effects of reversing agents (see PRECAUTIONS).
Children
The intravenous dose of succinylcholine is 2 mg/kg for infants and small children; for older children and adolescents the dose is 1 mg/kg (see WARNINGS and PRECAUTIONS-Pediatric Use).
Rarely, I.V. bolus administration of succinylcholine in infants and children may result in malignant ventricular arrhythmias and cardiac arrest secondary to acute rhabdomyolysis with hyperkalemia. In such situations, an underlying myopathy should be suspected.
Intravenous bolus administration of succinylcholine in infants and young children may result in profound bradycardia or, rarely, asystole. Unlike in adults, the incidence of bradycardia in infants and children is greater after a single dose of succinylcholine. The occurrence of bradyarrhythmias, in most cases, will be reduced by pretreatment with an anticholinergic drug (e.g. atropine) (see PRECAUTIONS – Pediatric Use).
Intramuscular Use
If necessary, succinylcholine may be given intramuscularly to infants, older children or adults when a suitable vein is inaccessible. A dose of up to 3 or 4 mg/kg may be given, but not more than 150 mg total dose should be administered by this route. The onset of effect of succinylcholine given intramuscularly is usually observed in about 2 to 3 minutes.
PHARMACEUTICAL INFORMATION
Drug Substance
Trade Name Succinylcholine Chloride Injection USP
Proper Name Succinylcholine chloride
Chemical Name 2,2’-[1,4-dioxo-1,4-butanediyl)bis(oxy)]bis[N,N,N,-trimethylethanaminium]dichloride
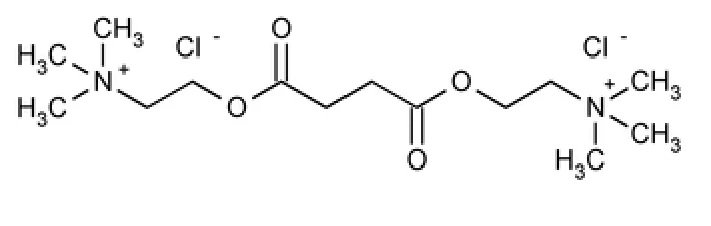
Structural Formula
Molecular Formula C14H30Cl2N2O4
Molecular Weight 361.31 g/mol
Description Succinylcholine chloride is a white, odorless, slightly bitter powder, that is very soluble in water. It is unstable in alkaline solutions, but relatively stable in acid solutions, depending upon the concentration of the solution and the storage temperature.
Stability - Compatibility
Succinylcholine is acidic (pH=3.5) and should not be mixed with alkaline solutions having a pH greater than 8.5 (e.g., barbiturate solutions).
Succinylcholine is rapidly hydrolyzed, quickly loses potency, and may cause a precipitate to form when mixed with alkaline solutions of other drugs. Preferably, succinylcholine should be separately injected and should not be mixed in the same syringe nor administered simultaneously through the same needle with solutions of short-acting barbiturates, such as Pentothal (sodium thiopental) or other drugs which have an alkaline pH.
Admixtures containing 1 to 2 mg per mL of succinylcholine may be prepared by diluting succinylcholine with a sterile solution, such as 5% Dextrose Injection, USP or 0.9% Sodium Chloride Injection, USP. Such admixtures should be used within 24 hours after preparation. Aseptic techniques should be used to prepare the diluted product. Admixtures of succinylcholine should be prepared for single patient use only. The unused portion of the diluted succinylcholine should be discarded.
Storage Recommendations
Succinylcholine Chloride Injection USP in multidose vials must be kept refrigerated (2 to 8°C) to prevent loss of potency. These products are stable for up to 28 days after first puncture without significant loss of potency, if stored at 2 – 8°C.
Availability
Succinylcholine Chloride Injection USP is supplied as a sterile solution in 10mL and 20mL multidose vials with rubber stopper.
Each mL of sterile solution contains: succinylcholine chloride (anhydrous base) 20 mg equivalent to 22 mg dihydrate, sodium chloride (for isotonicity), and hydrochloric acid (pH adjustment). Also contains methylparaben (1.8 mg/mL) and propylparaben (0.2 mg/mL) as preservatives.
MORE INFORMATION
If you want more information about Succinylcholine Chloride Injection USP:
- Talk to your healthcare professional
- Find the full Prescribing Information that is prepared for healthcare professionals by visiting the Health Canada website (https://www.canada.ca/en/health-canada/services/drugs-health-products/drug-products/drug-product-database.html); or by calling 1-800-656-0793
Last revised: October 7, 2024
REFERENCES
- 1. Assem ESK. Anaphylactic reactions affecting the human heart. Agents and Actions 1989; 27:142.
- 2. Carrol JB. Increased incidence of masseter spasm in children with strabismus anesthetized with halothane and succinylcholine. Anesthesiology 1987; 67:559-561.
- 3. Crespi G, Lualdi M, Restelli L, Pellerin I, Castiglioni C. Halothane and isoflurane: succinylcholine-induced heart rate changes in pediatric anaesthesia. Minerva Anestesiol 1988; 54:1-4.
- 4. Delphin E, Jackson D, Rothstein P. Use of succinylcholine during elective pediatric anesthesia should be reevaluated. Anesth Analg 1987; 66:1190-2.
- 5. Futter ME, Donati F, Bevan DR. Prolonged suxamethonium infusion during nitrous oxide anaesthesia supplemented with halothane or fentanyl. Br J Anaesth 1983; 55:947-53.
- 6. Goudsouzian NG. Relaxants in paediatric anaesthesia. Clin Anaesthesiol 1985; 3(3):539-51.
- 7. Gronert GA. Malignant hyperthermia. Anesthesiology 1980; 53(5):395-423.
- 8. Gronert GA, Theye RA. Pathophysiology of hyperkalemia induced by succinylcholine. Anesthesiology 1973; 43(1):89-99.
- 9. Gürgey A. Malignant hyperthermia in a patient with sickle cell anemia. Turk J Pediatr 1989; 31:245-247.
- 10. Illes IA, Defensor NC. Incidence and detection of cardiac arrhythmias during halothane anesthesia. Anesth Analg 1965; 44:529-531.
- 11. Kashimoto S, Kanda F, Kumazawa T. Succinylcholine-induced ventricular arrythmia during halothane anesthesia. Resuscitation 1985; 12:233-236.
- 12. Knight J, Mercader M, Bebak D. Anaphylaxis to succinylcholine. J Kans Med Soc 1982; 83:424.
- 13. List WFM. Succinylcholine-induced cardiac arrhythmias. Anesth Analg 1971; 50:361-367.
- 14. Mehler J, Bachour H, Simons F, Wolpers K. Cardiac arrest during induction of anesthesia with halothane and succinylcholine in an infant. Severe hyperkalemia and rhabdomyolysis due to a suspected myopathy and/or malignant hyperthermia. Anaesthesist 1991; 40:497-501.
- 15. Nash CL, Haller R, Brown RH. Succinylcholine, paraplegia, and intra-operative cardiac arrest. A Case Report. J Bone Joint Surg 1981; 63A(6):1010-2.
- 16. Rosenberg H, Gronert GA. Intractable cardiac arrest in children given succinylcholine. Anesthesiology 1992; 77(5):1054.
- 17. Stoelting RK. Comparison of gallamine and atropine as pretreatment before anesthetic induction and succinylcholine administration. Anesth Analg 1977; 56:493-495.
- 18. Warner LO, Beach TP, Garvin JP, Warner EJ. Halothane and children: The first quarter century. Anesth Analg 1984; 63:838-840.
- 19. Pfizer Canada ULC, Prescribing Information, Quelicin®,Control Number: 280413, Feb 26, 2024.