


Product Monograph - Sulfatrim Pediatric
Recent Major Label Changes
| 2 Contraindications | 2025-01 |
|---|---|
| 3 Serious Warnings and Precautions Box | 2025-01 |
| 7 Warnings and Precautions, General | 2025-01 |
| 7 Warnings and Precautions, Immune | 2025-01 |
| 7 Warnings and Precautions, Respiratory | 2026-07 |
Table of Contents
Certain sections or subsections that are not applicable at the time of the preparation of the most recent authorized product monograph are not listed.
Recent Major Label Changes .................................................................................................... 2
Table of Contents .................................................................................................................... 2
Part 1: Healthcare Professional Information ............................................................................ 4
- 1.
Indications .......................................................................................................................... 4
1.1. Pediatrics ................................................................................................................... 5
1.2. Geriatrics ................................................................................................................... 6
- 2. Contraindications ............................................................................................................ 6
- 3. Serious Warnings and Precautions Box ............................................................................ 7
- 4.
Dosage and Administration ............................................................................................. 7
4.2. Recommended Dose and Dosage Adjustment .......................................................... 7
- 5. Overdose ............................................................................................................................ 9
- 6. Dosage Forms, Strengths, Composition, and Packaging .................................................. 10
- 7.
Warnings and Precautions .............................................................................................. 11
7.1. Special Populations ................................................................................................. 17
7.1.1. Pregnancy ................................................................................................................ 17
7.1.2. Breastfeeding .......................................................................................................... 17
7.1.3. Pediatrics ................................................................................................................. 18
7.1.4. Geriatrics ................................................................................................................. 18
- 8.
Adverse Reactions .......................................................................................................... 19
8.1. Adverse Reaction Overview ..................................................................................... 19
- 9.
Drug Interactions ............................................................................................................ 21
9.1. Serious Drug Interactions ........................................................................................ 21
9.3. Drug-Behaviour Interactions ................................................................................... 21
9.4. Drug-Drug Interactions ............................................................................................ 21
9.5. Drug-Food Interactions............................................................................................ 23
9.6. Drug-Herb Interactions ............................................................................................ 23
9.7. Drug-Laboratory Test Interactions .......................................................................... 24
- 10.
Clinical Pharmacology ................................................................................................ 24
10.1. Mechanism of Action ............................................................................................... 24
10.3. Pharmacokinetics .................................................................................................... 25
- 11. Storage, Stability, and Disposal ....................................................................................... 27
Part 2: Scientific Information ................................................................................................. 28
- 13. Pharmaceutical Information ............................................................................................ 28
- 14.
Clinical Trials ............................................................................................................... 29
14.2. Comparative Bioavailability Studies ........................................................................ 29
- 15. Microbiology .................................................................................................................. 30
- 16. Non-Clinical Toxicology ................................................................................................... 36
- 17. Supporting Product Monographs .................................................................................... 39
Patient Medication Information ............................................................................................ 41
Part 1: Healthcare Professional Information
1. Indications
SULFATRIM (sulfamethoxazole and trimethoprim tablets) is indicated for treatment of infections associated with the following gram-positive and gram-negative organisms:
Gram-Negative Organisms
Haemophilus influenzae
Neisseria gonorrhoeae
Escherichia coli
Klebsiella species
Enterobacter (Aerobacter) aerogenes
Proteus mirabilis
Proteus vulgaris
Salmonella species
Shigella species
Vibrio cholerae
Gram-Positive Organisms
Streptococcus pyogenes
Streptococcus viridans
Staphylococcus albus
Staphylococcus aureus
Diplococcus pneumoniae
Other Organisms
Brucella melitensis
Nocardia asteroides
Nocardia brasiliensis
Paracoccidioides brasiliensis
Pneumocystis jiroveci
Streptomyces somaliensis
Sensitivity tests should be performed wherever possible to determine choice of therapy. These tests should be repeated if there is a failure to respond, relapse or early recurrence.
SULFATRIM may be indicated for the following infections when caused by susceptible strains of the above organisms.
Urinary Tract Infections:
Treatment of acute uncomplicated urinary tract infections*. It is recommended that initial episodes of uncomplicated urinary tract infections be treated with a single effective antibacterial agent rather than the combination.
Upper and Lower Respiratory Tract Infections:
Treatment of acute exacerbations of chronic bronchitis.
Treatment of Pneumocystis jiroveci pneumonia*. SULFATRIM is also indicated in the treatment of infants and children with a diagnosis of Pneumocystis jiroveci pneumonitis, especially if they are immunosuppressed.
Gastrointestinal Tract Infections:
Treatment of cholera, as an adjunct to fluid and electrolyte replacement, when the organism has been shown to be sensitive in vitro.
Treatment of bacillary dysentery*.
Other Infections:
Treatment of nocardiosis*. Brucellosis (second line therapy), when used in combination with gentamicin or rifampicin.
SULFATRIM is not indicated in infections associated with Pseudomonas, Mycoplasma, nor when the infection is caused by a virus.
This drug has not yet been fully evaluated in streptococcal infections.
*Sulfamethoxazole and trimethoprim has been investigated clinically in these indications.
To reduce the development of drug-resistant bacteria and maintain the effectiveness of SULFATRIM and other antibacterial drugs, SULFATRIM should be used only to treat infections that are proven or strongly suspected to be caused by susceptible bacteria. When culture and susceptibility information are available, they should be considered in selecting or modifying antibacterial therapy. In the absence of such data, local epidemiology and susceptibility patterns may contribute to the empiric selection of therapy.
1.1. Pediatrics
Pediatrics (< 2 months of age): Based on the data submitted and reviewed by Health Canada, the safety and efficacy of sulfamethoxazole and trimethoprim in pediatric patients (< 2 months) has not been established; therefore SULFATRIM is not recommended for pediatric patients younger than 2 months of age (see 2 Contraindications).
Pediatrics (2 months – 12 years of age): Based on the data submitted and reviewed by Health Canada, the safety and efficacy of sulfamethoxazole and trimethoprim in pediatric patients (2 months – 12 years of age) has been established; therefore, Health Canada has authorized an indication for pediatric use.
Consult specific dosing guidelines for pediatrics 2 months–12 years of age in 4.2. Recommended Dose and Dosage Adjustment.
Adolescents (>12–17 years of age): The recommended doses for adults should be used in adolescent patients (>12–17 years of age) (see 4.2. Recommended Dose and Dosage Adjustment).
1.2. Geriatrics
Geriatrics: Based on the data submitted and reviewed by Health Canada, the safety and efficacy of sulfamethoxazole and trimethoprim in geriatric patients has been established; therefore, Health Canada has authorized an indication for geriatric use. However, there may be an increased risk of severe adverse reactions in elderly patients, particularly when complicating conditions exist (see 7 Warnings and Precautions and 8 Adverse Reactions). Appropriate dosage adjustments should be made (see 4 Dosage and Administration).
2. Contraindications
SULFATRIM:
- is contraindicated in patients who are hypersensitive to this drug or to any ingredient in the formulation, including any non-medicinal ingredient, or component of the container. For a complete listing (see 6 Dosage Forms, Strengths, Composition and Packaging).
- is contraindicated in patients with a history of drug-induced immune thrombocytopenia, with use of trimethoprim and/or sulfonamides, and in patients with documented megaloblastic anemia due to folate deficiency, evidence of marked parenchymal damage, or blood dyscrasias.
- is contraindicated in patients with marked renal impairment where repeated measurements monitoring plasma drug concentrations cannot be performed (see 7 Warnings and Precautions).
- is contraindicated in pregnant patients and in nursing mothers, because sulfonamides pass the placenta and are excreted in the milk and may cause kernicterus.
- is contraindicated in premature babies and full-term infants less than two months of age.
- should not be given to patients with acute porphyria.
- must not be given in combination with dofetilide (see 9 Drug Interactions).
3. Serious Warnings and Precautions Box
|
|---|
4. Dosage and Administration
4.2. Recommended Dose and Dosage Adjustment
| Indication | Dosage* | Duration of Therapy | |
|---|---|---|---|
| Indication | Dosage* | Duration of Therapy | |
Adults & Children over 12 years # of tablets | Children 12 years of age and under mg/kg | ||
Adults & Children over 12 years # of tablets | Children 12 years of age and under mg/kg | ||
| Bacterial Infections | 2 SULFATRIM tablets or 1 SULFATRIM DS tablet b.i.d. | 15 mg SMZ / kg & 3 mg TMP / kg b.i.d. | At least 5 days or until patient is asymptomatic for 48 hours. |
| Severe Bacterial Infections | 3 SULFATRIM tablets or 1 ½ SULFATRIM DS tablet b.i.d. | Urinary infections: until the urine becomes sterile. | |
| Prophylaxis and Salmonella Carriers | 1 SULFATRIM tablet or ½ SULFATRIM DS tablet b.i.d. | Acute Salmonellosis: at least 7 days after defervescence. | |
| Salmonella carriers: until repeated stool cultures are negative. | |||
| Uncomplicated Gonorrhea | 2 SULFATRIM tablets or 1 SULFATRIM DS tablet q.i.d. | Two days. | |
| Pneumocystis jiroveci Pneumonitis | 25 mg SMZ / kg & 5 mg TMP / kg q.i.d. | At least 14 days. | |
| * SMZ = sulfamethoxazole, TMP = trimethoprim | |||
Serious Systemic Infections
Children:
Treatment should be continued until the patient has been symptom free for 2 days; the majority will require treatment for at least 5 days.
Other diseases, including certain tropical diseases rarely seen in Canada have also been successfully treated with sulfamethoxazole and trimethoprim. The duration of treatment is as follows:
| Disease | Duration |
| Cholera | 7 days |
| Nocardiosis | 12 weeks |
| Brucellosis | 2 weeks to 3 months |
Pneumocystis jiroveci Pneumonitis
Children and Adults:
Therapy should be continued for a total treatment period of at least two weeks. The aim is to obtain peak plasma or serum levels of trimethoprim of greater than or equal to 5 micrograms / mL.
Patients with Impaired Renal Function
When renal function is impaired, a reduced dosage should be employed using the following table:
| Creatinine Clearance (mL / min) | Recommended Dose Regimen |
Above 25 15-25 Below 15 | Usual standard regimen Half the usual regimen Use not recommended |
5. Overdose
Symptoms and Treatment
Acute:
The amount of a single dose of sulfamethoxazole and trimethoprim that is either associated with symptoms of overdosage or is likely to be life-threatening has not been reported. Signs and symptoms of overdosage reported with sulfonamides include anorexia, colic, nausea, vomiting, dizziness, headache, drowsiness, and unconsciousness. Pyrexia, hematuria, and crystalluria may be noted. Blood dyscrasias and jaundice are potential late manifestations of overdosage. Signs of acute overdosage with trimethoprim include nausea, vomiting, dizziness, headache, mental depression, confusion, and bone marrow depression.
General principles of treatment include the forcing of oral fluids; and the administration of intravenous fluids if urine output is low and renal function is normal. Acidification of the urine will increase renal elimination of trimethoprim. Inducing diuresis plus alkalinisation of urine will enhance the elimination of sulfamethoxazole. Alkalinisation will reduce the rate of elimination of trimethoprim. The patient should be monitored with blood counts and appropriate blood chemistries, including electrolytes. If a significant blood dyscrasia or jaundice occurs, specific therapy should be instituted for these complications. Peritoneal dialysis is not effective and hemodialysis is only moderately effective in eliminating trimethoprim and sulfamethoxazole.
There is no known antidote for sulfonamide poisoning; however, calcium folinate (leucovorin), 3 to 6 mg intramuscular (I.M.) for 5 to 7 days, is an effective antidote for adverse effects in the hemopoietic system caused by trimethoprim.
Chronic:
Use of SULFATRIM at high doses and/or for extended periods of time may cause confusion and bone marrow depression manifested as thrombocytopenia, leukopenia, and/or megaloblastic anemia. If signs of bone marrow depression occur, the patient should be given leucovorin; 5 to 15 mg leucovorin daily has been recommended by some investigators.
| For the most recent information in the management of a suspected drug overdose, contact your regional poison control centre or Health Canada’s toll-free number, 1-844 POISON-X (1-844-764-7669). |
|---|
- 6. Dosage Forms, Strengths, Composition, and Packaging
Table 1 – Dosage Forms, Strengths, Composition and Packaging
| Route of Administration | Dosage Form / Strength / Composition | Non-medicinal Ingredients |
|---|---|---|
| Oral | Tablets, 400 mg / 80 mg, 800 mg / 160 mg and 100 mg / 20 mg | Colloidal silicon dioxide, croscarmellose sodium, magnesium stearate and methylcellulose. |
SULFATRIM Tablets: Each white, round tablet, one side convex, other side FFBE, scored and engraved APO over 400-80 on the convex side, and other side plain contains 400 mg sulfamethoxazole and 80 mg trimethoprim. Available in bottles of 100.
SULFATRIM DS Tablets: Each white, capsule-shaped, biconvex tablet, partially bisected and engraved APO-DS on one side, and other side plain contains 800 mg sulfamethoxazole and 160 mg trimethoprim. Available in bottles of 500.
SULFATRIM PEDIATRIC Tablets: Each white, round, flat-faced beveled edge tablet scored and engraved APO over PED one side, other side plain, contains 100 mg sulfamethoxazole and 20 mg trimethoprim. Available in bottles of 100.
7. Warnings and Precautions
General
SULFATRIM should only be used where, in the judgement of the physician, the benefit of treatment outweighs any possible risks; consideration should be given to the use of a single effective antibacterial agent.
SULFATRIM should be given with caution to patients with impaired renal or hepatic function, to those with possible folate deficiency (e.g., the elderly, chronic alcoholics, rheumatoid arthritics, patients receiving anticonvulsant therapy, patients with malabsorption syndrome, and patients in malnutrition states), and to those with severe allergy or bronchial asthma.
The possibility of superinfection with a non-sensitive organism should be borne in mind.
Life-threatening adverse reactions
Fatalities associated with the administration of sulfonamides and sulfamethoxazole and trimethoprim, although rare, have occurred due to severe reactions, including Stevens-Johnson syndrome (SJS), toxic epidermal necrolysis (TEN), drug reaction with eosinophilia and systemic symptoms (DRESS), acute febrile neutrophilic dermatosis (Sweet’s syndrome), acute generalised exanthematous pustulosis (AGEP), fulminant hepatic necrosis, agranulocytosis, immune thrombocytopenia, aplastic anemia, other blood dyscrasias, and hypersensitivity of the respiratory tract (see 3 Serious Warnings and Precautions Box).
Circulatory shock with fever, severe hypotension, and confusion requiring intravenous fluid resuscitation and vasopressors has occurred within minutes to hours of re-challenge with trimethoprim-sulfamethoxazole in patients with history of recent (days to weeks) exposure to sulfamethoxazole-trimethoprim.
Driving and Operating Machinery
Due caution should be exercised when driving or operating a vehicle or potentially dangerous machinery.
Endocrine and Metabolism
Metabolic acidosis
Trimethoprim-sulfamethoxazole has been associated with metabolic acidosis when other possible underlying causes have been excluded. Close monitoring is always advisable when metabolic acidosis is suspected.
Fluid overload
Fluid overload is possible, especially when very high doses are being administered to patients with underlying cardio-pulmonary disease.
Urinary output
An adequate urinary output should be maintained at all times. Evidence of crystalluria in vivo is rare, although sulfonamide crystals have been noted in cooled urine from treated patients. In patients suffering from hypoalbuminaemia the risk may be increased.
Patients with hyperkalaemia and hyponatraemia
Caution should be exercised in administering trimethoprim to patients at risk of hyperkalemia and hyponatremia. Serum potassium and sodium and renal function should be closely monitored, and dosage should be adjusted for renal function (see 7 Warnings and Precautions - Renal and 4.2 Recommended Dose and Dosage Adjustment).
The risk factors for hyperkalemia are high trimethoprim dosage (20 mg / kg / day), renal insufficiency (serum creatinine ≥ 1.2 mg / dl), hypoaldosteronism, older age, dietary potassium and other drugs that impair potassium excretion. The likely mechanism is via trimethoprim inhibition of sodium channels in the distal nephron, similar to that of the potassium-sparing diuretic amiloride.
Hyperkalemia is generally reversible on discontinuation of trimethoprim. In patients presented with hyperkalemia due to SULFATRIM, SULFATRIM can be discontinued and appropriate standard potassium-lowering therapy instituted.
Phenylketonuric Patients
Trimethoprim has been noted to impair phenylalanine metabolism but this is of no significance in phenylketonuric patients on appropriate dietary restriction.
Gastrointestinal
Clostridioides difficile – Associated Disease (CDAD)
Clostridioides difficile-associated disease (CDAD) has been reported with use of many antibacterial agents, including sulfamethoxazole and trimethoprim. CDAD may range in severity from mild diarrhea to fatal colitis. It is important to consider this diagnosis in patients who present with diarrhea, or symptoms of colitis, pseudomembranous colitis, toxic megacolon, or perforation of colon subsequent to the administration of any antibacterial agent. CDAD has been reported to occur over 2 months after the administration of antibacterial agents.
Treatment with antibacterial agents may alter the normal flora of the colon and may permit overgrowth of C. difficile. Clostridioides difficile produces toxins A and B, which contribute to the development of CDAD. CDAD may cause significant morbidity and mortality. CDAD can be refractory to antimicrobial therapy.
If the diagnosis of CDAD is suspected or confirmed, appropriate therapeutic measures should be initiated. Mild cases of CDAD usually respond to discontinuation of antibacterial agents not directed against C. difficile. In moderate to severe cases, consideration should be given to management with fluids and electrolytes, protein supplementation, and treatment with an antibacterial agent clinically effective against C. difficile.
Surgical evaluation should be instituted as clinically indicated, as surgical intervention may be required in certain severe cases (see 8 Adverse Reactions).
Patients with gastrointestinal tract infection
Clinicians should be aware that first line therapy in the management of all patients with diarrheal disease is the maintenance of adequate hydration.
Hematologic
SULFATRIM can cause agranulocytosis, where the number of white cells in the blood becomes dangerously low. Symptoms of this can include pyrexia, chills, oropharyngeal pain, asthenia. Patients can also experience fast heart rate or fast breathing. If patients experience any of these symptoms, the treatment with SULFATRIM should be immediately stopped.
SULFATRIM can cause aplastic anemia, where the bone marrow is unable to make enough blood cells from being damaged. Symptoms of this can include fatigue, dyspnoea, pallor, contusion, pyrexia, chills, oropharyngeal pain, and malaise. If patients experience any of these symptoms, the treatment with SULFATRIM should be immediately stopped.
Folate
Regular monthly blood counts are advisable when trimethoprim-sulfamethoxazole is given for long periods, or to folate deficient patients or to the elderly, since there exists a possibility of asymptomatic changes in haematological laboratory indices due to lack of available folate. Supplementation with folinic acid may be considered during treatment but this should be initiated with caution due to possible interference with antimicrobial efficacy (see 9.4. Drug-Drug Interactions). Changes indicative of folic acid impairment have, in certain specific situations, been reversed by folinic acid therapy.
Special care should be exercised when treating suspected folate-deficient patients; folate supplementation should be considered.
Patients with serious haematological disorders
Except under careful supervision trimethoprim-sulfamethoxazole should not be given to patients with serious hematological disorders (see 8 Adverse Reactions).
Hepatic/ Biliary/ Pancreatic
SULFATRIM can cause fulminant hepatic necrosis that may be life-threatening. Symptoms include jaundice, upper right abdominal pain, abdominal distension, nausea and vomiting. If patients experience any of these symptoms, the treatment with SULFATRIM should be immediately stopped.
Immune
Haemophagocytic lymphohistiocytosis:
Cases of haemophagocytic lymphohistiocytosis (HLH) have been reported very rarely in patients treated with sulfamethoxazole-trimethoprim (see 8.1. Adverse Reaction Overview). HLH is a life-threatening syndrome of pathologic immune activation characterized by clinical signs and symptoms of extreme systemic inflammation (e.g. fever, hepatosplenomegaly, hypertriglyceridaemia, hypofibrinogenaemia, high serum ferritin, cytopenias and haemophagocytosis) and is associated with high mortality rates if not recognized early and treated.
- Immediately evaluate patients who develop early manifestations of pathologic immune activation.
- If HLH is diagnosed, discontinue sulfamethoxazole-trimethoprim treatment.
Use in the Treatment of and Prophylaxis for Pneumocystis jiroveci Pneumonia in Patients with Acquired Immunodeficiency Syndrome (AIDS):
The incidence of side effects, particularly rash, severe hypersensitivity reactions, fever, leukopenia, neutropenia, thrombocytopenia and elevated aminotransferase (transaminase) values in AIDS patients who are being treated with sulfamethoxazole and trimethoprim for Pneumocystis jiroveci pneumonia (PJP) has been reported to be greatly increased compared with the incidence normally associated with the use of sulfamethoxazole and trimethoprim in non-AIDS patients. If signs of bone marrow depression occur, the patient should be given calcium folinate supplementation (5 to 10 mg / day). The incidence of hyperkalemia and hyponatremia appears to be increased in AIDS patients receiving sulfamethoxazole and trimethoprim. Adverse effects are generally less severe in patients receiving sulfamethoxazole and trimethoprim for prophylaxis. A history of mild intolerance to sulfamethoxazole and trimethoprim in AIDS patients does not appear to predict intolerance of subsequent secondary prophylaxis. However, if a patient develops skin rash or any sign of adverse reaction, therapy with SULFATRIM should be re-evaluated (see 7 Warnings and Precautions). Rhabdomyolysis has been reported in HIV positive patients receiving trimethoprim-sulfamethoxazole for prophylaxis or treatment of PJP. In some cases, rhabdomyolysis led to acute renal failure requiring emergency dialysis.
Severe hypersensitivity reactions have also been reported in HIV-infected patients on re-exposure to sulfamethoxazole and trimethoprim, sometimes after a dosage interval of a few days. Concomitant administration of intravenous diphenhydramine may permit continued infusion.
The concomitant use of leucovorin with sulfamethoxazole and trimethoprim for the acute treatment of Pneumocystis jiroveci pneumonia in patients with HIV infection was associated with increased rates of treatment failure and morbidity in a placebo-controlled study (see 9.4 Drug-Drug Interactions).
Immune thrombocytopenia
SULFATRIM can cause immune thrombocytopenia that may be life-threatening. Symptoms of this include being easily bruised, a rash on the skin that appears tiny pinpoint- sized reddish or purple spots, usually on the lower legs, gingival bleeding or epistaxis, and blood in urine or haematochezia. If patients experience any of these symptoms, the treatment with SULFATRIM should be immediately stopped.
Monitoring and Laboratory Tests
SULFATRIM may affect the results of thyroid function tests.
Renal
In patients with renal impairment, a reduced or less frequent dosage is recommended in order to avoid accumulation of trimethoprim in the blood (see 4.2. Recommended Dose and Dosage Adjustment). Non-ionic diffusion is the main factor in the renal handling of trimethoprim, and as renal failure advances, trimethoprim excretion decreases. For such patients, serum assays are necessary. SULFATRIM should not be used when the serum creatinine level is above 2 mg per 100 mL, in order to avoid possible permanent impairment of renal function.
Patients with glucose-6-phosphate dehydrogenase deficiency
In glucose-6-phosphate dehydrogenase-deficient individuals, hemolysis may occur. This reaction is frequently dose-related.
Patients with or at risk of acute porphyria
The administration of SULFATRIM to patients known or suspected to be at risk of acute porphyria should be avoided. Both trimethoprim and sulfonamides (although not specifically sulfamethoxazole) have been associated with clinical exacerbation of acute porphyria.
Functional inhibition of the renal tubular secretion of creatinine may produce a spurious fall in the estimated rate of creatinine clearance.
Respiratory
Hypersensitivity reactions of the respiratory tract
SULFATRIM can cause an allergic reaction in the lungs and airways, where the airways can close up and make breathing difficult. This can be life-threatening if the person does not get medical help. Symptoms include dyspnea, cough, wheezing, and chest discomfort. If patients experience any of these symptoms, treatment with SULFATRIM should be immediately stopped.
Lung injury
Sulfatrim and trimethoprim has been associated with acute and delayed causes of respiratory toxicity, sometimes progressing to fulminant lung injury and acute respiratory distress syndrome (ARDS). Patients on SULFATRIM therapy should be monitored for signs and symptoms of lung injury, such as shortness of breath, cough, fever, dyspnea, and chest tightness. The onset of these pulmonary signs in association with radiological signs of pulmonary infiltrates and deterioration in pulmonary function may be preliminary signs of ARDS. In such circumstances, SULFATRIM should be discontinued and appropriate treatment given.
Severe pulmonary adverse reactions occurring within days to weeks of SULFATRIM treatment initiation and resulting in prolonged respiratory failure requiring mechanical ventilation or extracorporeal membrane oxygenation (ECMO), lung transplantation or death have been reported in patients and otherwise healthy individuals treated with trimethoprim- sulfamethoxazole products.
Sensitivity/Resistance
Development of Drug Resistant Bacteria
Prescribing SULFATRIM in the absence of a proven or strongly suspected bacterial infection is unlikely to provide benefit to the patient and risks the development of drug-resistant bacteria.
Treatment of streptococcal pharyngitis due to Group A beta-haemolytic streptococci
SULFATRIM should not be used in the treatment of streptococcal pharyngitis. Clinical studies have documented that patient with group A β-hemolytic streptococcal tonsillopharyngitis have a greater incidence of bacteriologic failure when treated with sulfamethoxazole and trimethoprim than to those patients treated with penicillin, as evidenced by failure to eradicate this organism from the tonsillopharyngeal area.
Skin
SULFATRIM can cause severe skin reactions that may be life-threatening, including: Steven-Johnson syndrome (SJS), toxic epidermal necrolysis (TEN), drug reaction with eosinophilia and systemic symptoms (DRESS), acute febrile neutrophilic dermatosis (Sweet’s syndrome) and acute generalised exanthematous pustulosis (AGEP). Symptoms include: rash erythematous, blister, skin exfoliation, pyrexia, body aches, eosinophilia, blisters and sores or ulcers on mucous membranes (mouth, nose and genitals), ocular hyperaemia and eye swelling. If patients experience any of these symptoms, the treatment with SULFATRIM should be immediately stopped.
Patients should be advised of the signs and symptoms and advised to monitor closely for skin reactions. The highest risk for occurrence of SJS or TEN is within the first weeks of treatment and of DRESS is within the first two to eight weeks after drug administration. The best results in managing SJS, TEN, DRESS, AGEP and Sweet’s syndrome come from early diagnosis and immediate discontinuation of any suspect drug. Early withdrawal is associated with a better prognosis. If the patient has developed SJS, TEN, DRESS, AGEP and Sweet’s syndrome with the use of SULFATRIM, SULFATRIM must not be re-started in this patient at any time.
7.1. Special Populations
7.1.1. Pregnancy
Trimethoprim and sulfamethoxazole cross the placenta and their safety in human pregnancy has not been established. Trimethoprim is a folate antagonist and, in animal studies, both agents have been shown to cause fetal abnormalities. At doses in excess of the recommended human therapeutic dose, trimethoprim and sulfamethoxazole have been reported to cause cleft palate and other fetal abnormalities in rats, findings typical of a folate antagonist. Effects with trimethoprim were preventable by administration of dietary folate. In rabbits, fetal loss was seen at doses of trimethoprim in excess of human therapeutic doses. Case-control studies have shown that there may be an association between exposure to folate antagonists and birth defects in humans. Therefore, SULFATRIM should be avoided in pregnancy, particularly in the first trimester, unless the potential benefit to the mother outweighs the potential risk to the fetus; folate supplementation should be considered if SULFATRIM is used in pregnancy.
Sulfamethoxazole competes with bilirubin for binding to plasma albumin. As significant maternally derived drug levels persist for several days in the newborn, there may be a risk of precipitating or exacerbating neonatal hyperbilirubinaemia, with an associated theoretical risk of kernicterus, when SULFATRIM is administered to the mother near the time of delivery. This theoretical risk is particularly relevant in infants at increased risk of hyperbilirubinaemia, such as those who are preterm and those with glucose-6-phosphate dehydrogenase deficiency.
7.1.2. Breastfeeding
Trimethoprim and sulfamethoxazole are excreted in breast milk. Administration of SULFATRIM should be avoided in late pregnancy and in lactating mothers where the mother or infant has, or is at particular risk of developing hyperbilirubinaemia. Additionally, administration of SULFATRIM should be avoided in infants younger than eight weeks in view of predisposition of young infants to hyperbilirubinaemia.
7.1.3. Pediatrics
Pediatrics (2 months–12 years of age): Based on the data submitted and reviewed by Health Canada, the safety and efficacy of sulfamethoxazole and trimethoprim in pediatric patients 2 months-12 years of age have been established; therefore, Health Canada has authorized an indication for pediatric use.
Pediatrics (<2 months of age): SULFATRIM is not authorized for pediatric patients younger than 2 months of age (see 2. Contraindications).
Adolescents (12–17 years of age): The recommended doses for adults should be used in adolescent patients (12–17 years of age) (see 4.2. Recommended Dose and Dosage Adjustment).
7.1.4. Geriatrics
Based on the data submitted and reviewed by Health Canada, the safety and efficacy of sulfamethoxazole and trimethoprim in geriatric patients have been established; therefore, Health Canada has authorized an indication for geriatric use. However, there may be an increased risk of severe adverse reactions in elderly patients, particularly when complicating conditions exist, e.g., impaired kidney and/or liver function, or concomitant use of other drugs. Severe skin reactions, or generalized bone marrow suppression (see 7 Warnings and Precautions and 8 Adverse Reactions), or a specific decrease in platelets (with or without purpura) are the most frequently reported severe adverse reactions in elderly patients. In those concurrently receiving certain diuretics, primarily thiazides, an increased incidence of thrombocytopenia with or without purpura has been reported. Appropriate dosage adjustments should be made for patients with impaired kidney function (see 4.2 Recommended Dose and Dosage Adjustment).
Close supervision is recommended when SULFATRIM is used in elderly patients or in patients taking high doses of SULFATRIM as these patients may be more susceptible to hyperkalemia and hyponatremia.
Special care should be exercised when treating the elderly or suspected folate-deficient patients; folate supplementation should be considered.
8. Adverse Reactions
8.1. Adverse Reaction Overview
The most common adverse effects are hyperkalemia, anorexia, monilial overgrowth, headache, gastrointestinal disturbances (nausea, vomiting, diarrhea) and allergic skin reactions (such as rash and urticaria). Fatalities associated with the administration of sulfonamides and sulfamethoxazole and trimethoprim, although rare, have occurred due to severe reactions, including Stevens-Johnson Syndrome (SJS), drug reaction with Eosinophilia and Systemic Symptoms (DRESS), Toxic Epidermal Necrolysis (TEN), fulminant hepatic necrosis, agranulocytosis, aplastic anemia, other blood dyscrasias, and hypersensitivity of the respiratory tract (See 3 Serious Warnings and Precautions Box and 7 Warnings and Precautions).
General
Weakness, fatigue, insomnia, vision troubles, alopecia, epistaxis, edema. Monilial overgrowth is common.
Allergic
Anaphylactic reaction, allergic myocarditis, erythema multiforme, toxicoderma, exfoliative dermatitis, angioedema, pyrexia, chills, hypersensitivity, vasculitis resembling Henoch-Schönlein purpura, serum sickness, serum sickness-like syndrome, generalized allergic reactions, generalized skin eruptions, fixed drug eruption, photosensitivity, conjunctival and scleral injection, pruritus, urticaria, and rash. In addition, periarteritis nodosa and systemic lupus erythematosus and anaphylactoid reactions (sweating and collapse) have been reported.
Severe hypersensitivity reactions associated with PJP including rash, pyrexia, neutropenia, thrombocytopenia, hepatic enzyme increased, rhabdomyolysis, hyperkalaemia, hyponatraemia have been reported at the high dosages used for PJP management, necessitating cessation of therapy.
Rhabdomyolysis has been reported in HIV positive patients receiving trimethoprim-sulfamethoxazole for prophylaxis or treatment of PJP.
Cardiovascular
QT interval prolongation (ventricular tachycardia).
Endocrine and Metabolism
The sulfonamides bear certain chemical similarities to some goitrogens, diuretics (acetazolamide and the thiazides), and oral hypoglycemic agents. Cross-sensitivity may exist with these agents. Diuresis and hypoglycemia have occurred rarely in patients receiving sulfonamides.
Decreased appetite, metabolic acidosis, renal tubular acidosis, hyperkalemia, hyponatremia, hypoglycemia (See 7 Warnings and Precautions).
Gastrointestinal
Pseudomembranous enterocolitis, pancreatitis, stomatitis, glossitis, dry mouth, nausea, vomiting, pyrosis, gastric intolerance, gastritis or gastroenteritis, dyspepsia emesis, abdominal pain, constipation, flatulence, diarrhea, tooth and/or tongue discolouration
Genitourinary
Impaired renal function (sometimes reported as renal failure), interstitial nephritis, kidney changes (as indicated by abnormal elevations in blood urea nitrogen, blood non-protein nitrogen, serum creatinine and urine protein levels), toxic nephrosis with oliguria and anuria, crystalluria, hematuria, urgency, and dysuria.
Hematologic
Haemophagocytic lymphohistiocytosis, leukopenia, neutropenia, thrombocytopenia, megaloblastic anaemia, aplastic and hemolytic anemia, methemoglobinemia, purpura, agranulocytosis, hypoprothrombinemia, eosinophilia, haemolysis in certain susceptible glucose-6-phosphate dehydrogenase (G6PD)-deficient patients, bone marrow depression, and circulatory shock.
Hepatic/Biliary/Pancreatic
Hepatitis, including cholestatic jaundice and hepatic necrosis, jaundice, elevation of serum transaminase, alkaline phosphatase and bilirubin.
Hepatic changes including fatalities have been recorded in at-risk patients. Cholestatic jaundice and hepatic necrosis may be fatal.
Musculoskeletal
Arthralgia, rhabdomyolysis and myalgia.
Neurologic
Aseptic meningitis, convulsions, peripheral neuritis, ataxia, tremor, vertigo, tinnitus, headache.
Aseptic meningitis was rapidly reversible on withdrawal of the drug, but recurred in a number of cases on re-exposure to either sulfamethoxazole and trimethoprim or to trimethoprim alone.
Ophthalmologic
Uveitis
Psychiatric
Hallucinations, depression, apathy, nervousness, dizziness, psychotic disorder.
Respiratory
Lung infiltration, cough, dyspnea, acute eosinophilic pneumonia, acute and delayed lung injury, interstitial lung disease, and acute respiratory failure.
Cases of fulminant respiratory failure have been reported, necessitating cessation of therapy (see 7 Warnings and Precautions, Respiratory).
Skin and subcutaneous tissue disorders
Severe cutaneous adverse reactions (SCARs). acute febrile neutrophilic dermatosis (Sweet’s syndrome) (Frequency Not Known). Acute generalized exanthematous pustulosis (AGEP) (Frequency Not Known).
Stevens-Johnson syndrome (SJS), toxic epidermal necrolysis (TEN), and drug reaction with eosinophilia and systemic symptoms (DRESS) (Frequency Not Known) have been reported to be life-threatening (see 7 Warnings and Precautions).
9. Drug Interactions
9.1. Serious Drug Interactions
|
|---|
9.3. Drug-Behaviour Interactions
Patients should be instructed to maintain an adequate fluid intake in order to prevent crystalluria and stone formation.
Patients should tell their physician of all dietary regimens and supplements.
9.4. Drug-Drug Interactions
Diuretics (thiazides): in elderly patients concurrently receiving certain diuretics, primarily thiazides, an increased incidence of thrombocytopenia with or without purpura has been reported.
Pyrimethamine: occasional reports suggest that patients receiving pyrimethamine at doses in excess of 25 mg weekly may develop megaloblastic anemia should sulfamethoxazole and trimethoprim be prescribed concurrently.
Zidovudine: in some situations, concomitant treatment with zidovudine may increase risk of hematological adverse reactions to SULFATRIM. If concomitant treatment is necessary, consideration should be given to monitoring of hematological parameters.
Lamivudine: administration of sulfamethoxazole and trimethoprim 800 mg / 160 mg causes a 40% increase in lamivudine exposure because of the trimethoprim component. Lamivudine has no effect on the pharmacokinetics of trimethoprim or sulfamethoxazole.
Warfarin: it has been reported that sulfamethoxazole and trimethoprim may prolong the prothrombin time in patients who are receiving the anticoagulant warfarin. This interaction should be kept in mind when SULFATRIM is given to patients already on anticoagulant therapy, and the coagulation time should be reassessed.
Phenytoin: SULFATRIM may inhibit the hepatic metabolism of phenytoin. Sulfamethoxazole and trimethoprim, given at a common clinical dosage, increased the phenytoin half-life by 39% and decreased the phenytoin metabolic clearance rate by 27%. When administering these drugs concurrently, one should be alert for possible excessive phenytoin effect. Close monitoring of the patient’s condition and serum phenytoin levels is advisable.
Methotrexate: sulfonamides can also displace methotrexate from plasma protein binding sites, thus increasing free methotrexate concentrations. Folate supplementation should be considered. If SULFATRIM is considered appropriate therapy in patients receiving other anti-folate drugs, a folate supplementation should be considered.
Digoxin: concomitant use of trimethoprim with digoxin has been shown to increase plasma digoxin levels in a proportion of elderly patients.
Hyperkalaemia: caution should be exercised in patients taking any other drugs that can cause hyperkalemia, for example ACE inhibitors, angiotensin receptor blockers and potassium sparing diuretics such as spironolactone. Concomitant use of trimethoprim-sulfamethoxazole (cotrimoxazole) may result in clinically relevant hyperkalaemia.
Cyclosporin: reversible deterioration in renal function has been observed in patients treated with sulfamethoxazole and trimethoprim and cyclosporin following renal transplantation.
When trimethoprim is administered simultaneously with drugs that form cations at physiological pH, and are also partly excreted by active renal secretion (e.g., procainamide, amantadine), there is the possibility of competitive inhibition of this process which may lead to an increase in plasma concentration of one or both of the drugs.
Sulphonylurea hypoglycemic agents: Interaction with sulphonylurea hypoglycemic agents is uncommon but potentiation has been reported.
Rifampicin: concurrent use of rifampicin and sulfamethoxazole and trimethoprim results in a shortening of the plasma half life of trimethoprim after a period of about one week. This is not thought to be of clinical significance.
Trimethoprim is an inhibitor of cytochrome P450 2C8 enzyme and may interact with other drugs that are primarily metabolized by the 2C8 isoform. Sulfamethoxazole is an inhibitor of cytochrome P450 2C9 and may interact with other drugs that are primarily metabolized by the 2C9 isoform.
Repaglinide: trimethoprim may increase the exposure of repaglinide which may result in hypoglycaemia.
Folinic acid: folinic acid supplementation has been shown to interfere with the antimicrobial efficacy of trimethoprim-sulfamethoxazole. This has been observed in Pneumocystis jiroveci pneumonia prophylaxis and treatment.
Azathioprine: There are conflicting clinical reports of interactions between azathioprine and trimethoprim-sulfamethoxazole, resulting in serious haematological abnormalities.
Dofetilide: Increased plasma levels of dofetilide have been reported after co-administration of trimethoprim and dofetilide. Dofetilide can cause serious ventricular arrhythmias associated with QT interval prolongation, including torsades de pointes, which are directly related to the dofetilide plasma concentration. Concomitant administration of dofetilide and trimethoprim is contraindicated (see 2 Contraindications).
Leucovorin: The concomitant use of leucovorin with sulfamethoxazole and trimethoprim for the acute treatment of Pneumocystis jiroveci pneumonia in patients with HIV infection was associated with increased rates of treatment failure and morbidity in a placebo-controlled study.
9.5. Drug-Food Interactions
Caution should be exercised in patients following potassium enriched dietary regimens (see 4.2 Recommended Dose and Dosage Adjustment).
9.6. Drug-Herb Interactions
Interactions with herbal products have not been established.
9.7. Drug-Laboratory Test Interactions
Sulfamethoxazole and trimethoprim, specifically the trimethoprim component, can interfere with a serum methotrexate assay as determined by the competitive binding protein technique (CBPA) when a bacterial dihydrofolate reductase is used as the binding protein. No interference occurs, however, if methotrexate is measured by a radioimmunoassay (RIA).
The presence of trimethoprim and sulfamethoxazole may also interfere with the Jaffé alkaline picrate reaction assay for creatinine, resulting in overestimations of about 10% in the range of normal values.
10. Clinical Pharmacology
10.1. Mechanism of Action
SULFATRIM is an antibacterial agent with a wide spectrum of activity. It contains two active antibacterial components, sulfamethoxazole and trimethoprim, which act synergistically on many species of bacteria.
Figure 1
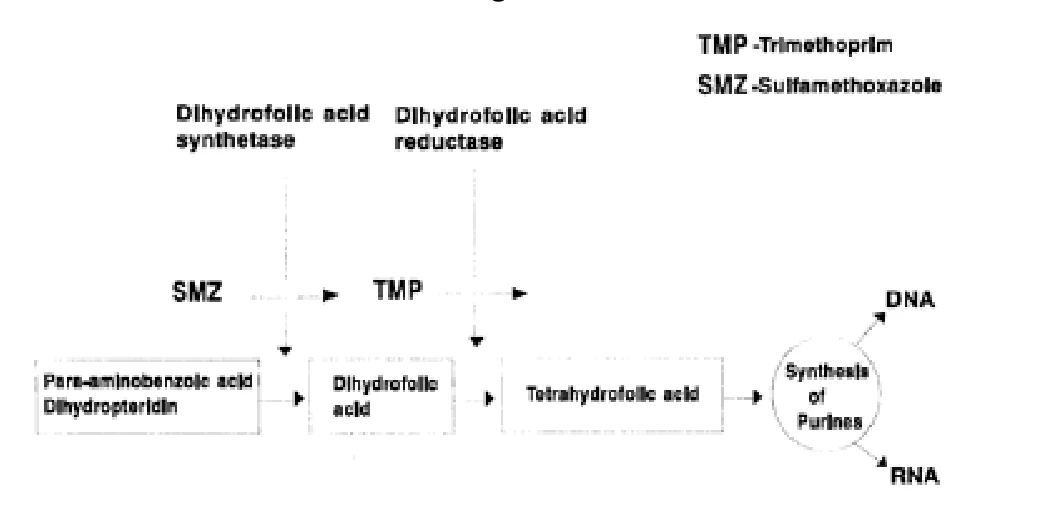
Sulfamethoxazole and trimethoprim act sequentially in two successive steps in the biosynthesis of nucleic acids. Trimethoprim is an inhibitor of dihydrofolate reductase, the enzyme which reduces dihydrofolic acid to its tetrahydro form. This biochemical step is essential in the production of the folate coenzymes which are involved in the biosynthesis of thymine, purine, serine and methionine. Sulfamethoxazole exerts its antibacterial activity by competing with para-aminobenzoic acid.
Most pathogenic bacteria meet their need for dihydrofolic acid by synthesizing it from para-aminobenzoic acid, pteridine and glutamic acid. Animals, in contrast, depend on exogenous sources for their needs of folic acid and do not rely upon intracellular synthesis.
Under usual circumstances, sulfamethoxazole or trimethoprim acting alone do not produce complete block in this biosynthesis of nucleic acids. Instead, they cause sufficient reduction in the synthesis of folate coenzymes to produce bacteriostasis. When the two agents act together, the superimposition of their effects produces a complete block in the synthesis, leading to death of the organism. Thus, the effect of the dual action is to reduce the minimum inhibitory concentrations (MIC) of each agent (synergism) and to convert a bacteriostatic action to a bactericidal action.
The activity of sulfamethoxazole and trimethoprim therefore depends upon the ability of both sulfamethoxazole and trimethoprim to affect the folate metabolism of the bacterium; however, for sulfamethoxazole and trimethoprim to be therapeutic it must not affect the folate metabolism of the host. Since sulfamethoxazole affects only the de novo synthesis of dihydrofolic acid by bacteria, it does not affect folate metabolism of animals. Since in animals, as in bacteria, the folates have to be recycled to the active form by dihydrofolate reductase, trimethoprim could be expected to affect mammalian folate metabolism. Trimethoprim, however, was especially selected from similar folate inhibitors because of its low toxicity for animals and high toxicity for bacteria. This difference has since been shown to be due to the fact that the affinity of trimethoprim for the dihydrofolate reductase of bacteria is some 40,000 times greater than for the corresponding mammalian enzyme.
10.3. Pharmacokinetics
The pharmacokinetic profiles of sulfamethoxazole and trimethoprim remain the same whether they are administered in combination or alone. Peak blood levels for both compounds occur one to four hours after oral administration. Detectable amounts are still present after 24 hours. The biological half-lives reported are 9 to 11 hours for sulfamethoxazole and 10 to 14 hours for trimethoprim.
Serum binding: In serum, the degree of protein-binding by trimethoprim varies with the concentration, but it normally is about 44% bound to plasma protein. Sulfamethoxazole was found to be about 70% bound to plasma protein. Addition of sulfamethoxazole reduced the binding of trimethoprim by 3 to 4%, but there was no change in the protein- binding of sulfamethoxazole at therapeutically attain able concentrations of the two drugs.
Absorption
Both trimethoprim and sulfamethoxazole are rapidly absorbed following oral administration. Detectable levels of both drugs appear in the blood in about five minutes with significant levels being reached within an hour. Peak blood levels for both compounds are attained usually in two to four hours, are maintained for about seven hours, and detectable amounts are still present after 24 hours. When the two drugs are administered together, the individual blood levels are similar to those achieved when the drugs are administered separately, thus indicating no effect in absorption of one drug by the other.
Distribution
The ratio of one part trimethoprim to five parts sulfamethoxazole achieves drug concentrations in the blood in the ratio of approximately 1:20, a ratio considered to be optimal against a wide range of bacteria. Unlike sulfamethoxazole, trimethoprim concentrates in tissues; biopsy material from a small number of patients taking trimethoprim preoperatively indicated that the concentration of trimethoprim in the tissues exceeded that of the plasma sampled at the same time - most significant in the lung (by 10 times). A similar pattern occurs in animals. Levels of trimethoprim in the sputum were also found to be higher than in the plasma following oral administration of trimethoprim-sulfamethoxazole. The concentrations of both drugs have also been found to be well-maintained in lymph and tissue fluids.
In serum, the degree of protein-binding by trimethoprim varies with the concentration, but it normally is about 44% bound to plasma protein. Sulfamethoxazole was found to be about 70% bound to plasma protein. Addition of sulfamethoxazole reduced the binding of trimethoprim by 3 to 4%, but there was no change in the protein-binding of sulfamethoxazole (about 66%) at therapeutically attainable concentrations of the two drugs.
Metabolism
Studies conducted on the individual components administered separately, indicate that in the presence of a high fluid intake, approximately 50%, and in the presence of a low fluid intake, approximately 40% of the orally ingested trimethoprim is excreted unchanged in the urine within 24 hours. Sulfamethoxazole is more extensively metabolised than TMP, via acetylation, oxidation or glucuronidation. Over a 72 hour period, approximately 85% of the dose can be accounted for in the urine as unchanged drug plus the major (N4- acetylated) metabolite. Approximately 10% of the excreted drug is in the form of metabolites with little or no antibacterial activity. Some trimethoprim is excreted in the bile, where concentrations twice those of plasma are obtained, but as it is almost completely reabsorbed; very little appears in the feces. Studies with radio-labelled trimethoprim indicated that it is almost completely absorbed following oral administration in man; less than 4% of the radioactivity appeared in the feces over a period of six days. Radioactivity was eliminated from the plasma and urine at almost identical rates; almost all of an oral dose being excreted in the urine within 48 hours. The biological half-life of trimethoprim was calculated to be 10 hours (range of 6.2 to 12 hours in four patients), which corresponds well to the half-life of 9 to 11 hours determined in man for sulfamethoxazole.
Elimination
From 25% to 50% of the orally ingested sulfamethoxazole is excreted in the urine within 24 hours. Of the excreted drug, approximately half is the N4 acetylated derivative, a fifth is the N4 conjugate, a sixth is the unchanged parent compound, and about a tenth is another N4 free compound.
Although the amount of each drug excreted is similar when given separately or in combination, the method of excretion by the kidney is quite different. Sharpstone demonstrated that there is net tubular reabsorption of filtered sulfamethoxazole, at least in patients with normal renal function, whereas with trimethoprim there is a tubular secretory mechanism of excretion in patients with normal or impaired renal function.
Renal clearance of sulfamethoxazole increased with rising urine flow-rate, was independent of urine pH when this was less than 7, but increased with alkalinization of the urine above a pH of 7. The clearance of trimethoprim was unaffected by alteration in urine flow-rate but increased sharply with falling urine pH.
Special Populations and Conditions
- Pediatrics See 4.2 Recommended Dose and Dosage Adjustment.
- Geriatrics In older patients, a slight reduction in renal clearance of sulfamethoxazole but not trimethoprim has been observed.
- Pregnancy and Breast-feeding See 7.1 Special Populations
- Hepatic Insufficiency Caution should be exercised when treating patients with severe hepatic impairment as this may decrease the absorption and biotransformation of trimethoprim and sulfamethoxazole.
- Renal Insufficiency In patients with impaired renal function, sulfamethoxazole excretion was only slightly decreased, whereas trimethoprim excretion decreased markedly in severe renal impairment.
- Storage, Stability, and Disposal
SULFATRIM tablets should be stored at room temperature between 15°C to 30°C and protected from light.
Keep out of reach and sight of children.
Part 2: Scientific Information
13. Pharmaceutical Information
Drug Substance
The active ingredients of SULFATRIM are a combination of trimethoprim and sulfamethoxazole which has been established in a ratio of 1:5.
Non-proprietary name of the drug substancee: Sulfamethoxazole
Chemical name: N1-(5 - methyl - 3 - isoxazolyl) sulfanilamide
Molecular formula and molecular mass: C10H11N3O3S 253.31 g/mol
Structural formula:
Physicochemical properties: Sulfamethoxazole is a white to off-white, practically odourless, crystalline compound. It has a melting point of 167°C.
Drug Substance
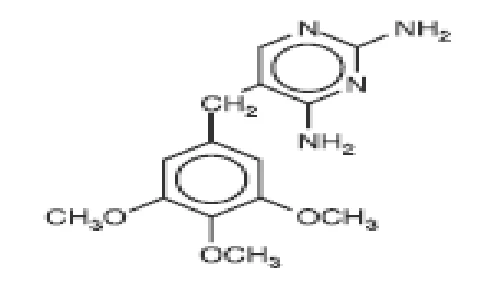
Non-proprietary name of the drug substance: Trimethoprim
Chemical name: 2,4 - diamino - 5 - (3,4,5 - trimethoxabenzyl) pimidine
Molecular formula and molecular mass: C14H18N4O3 290.32 g/mol
Structural formula:
 |
 |
Physicochemical properties: Trimethoprim is a white to cream, bitter crystalline powder. It has a melting point of 199 to 203°C and a solubility in water of 0.4 mg / mL.
14. Clinical Trials
Clinical trial information was not included in the Product Monograph at the time of initial authorization.
14.2. Comparative Bioavailability Studies
A single dose, two-way crossover comparative bioavailability study of SULFATRIM DS 800 mg sulfamethoxazole / 160 mg trimethoprim tablets (AA Pharma Inc.) and BACTRIM® DS 800 mg sulfamethoxazole / 160 mg trimethoprim tablets (Hoffmann-La Roche Limited) was conducted under fasting conditions in healthy male volunteers. The results obtained from 18 volunteers who completed the study are summarized in the following tables.
Table 2 - Summary Table of the Comparative Bioavailability Data
Sulfamethoxazole (1 x 800 mg sulfamethoxazole / 160 mg trimethoprim) Geometric Mean Arithmetic Mean (CV %) | ||||
|---|---|---|---|---|
| Parameter | Test1 | Reference2 | % Ratio of Geometric Means | 90% Confidence Interval |
AUCT (mcg·h/mL) | 530.42 534.22 (12.27) | 555.27 559.86 (13.39) | 95.5 | 92.3 - 98.9 |
AUCI (mcg·h/mL) | 580.94 585.94 (13.46) | 609.99 615.59 (14.12) | 95.2 | 92.0 - 98.6 |
Cmax (mcg /mL) | 42.15 42.35 (9.92) | 46.86 47.36 (14.64) | 89.9 | 84.0 - 96.3 |
Tmax3 (h) | 2.00 (1.00 - 6.00) | 1.50 (0.50 - 4.00) | ||
T1/24 (h) | 8.78 (9.43) | 9.11 (7.13) | ||
1 SULFATRIM DS (sulfamethoxazole and trimethoprim) tablets, 800 mg / 160 mg (AA Pharma Inc.)
2 BACTRIM® DS (sulfamethoxazole and trimethoprim) tablets, 800 mg / 160 mg (Hoffmann-La Roche Limited, Canada)
3 Expressed as the median (range) only
4 Expressed as the arithmetic mean (CV%) only
Table 3 - Summary Table of the Comparative Bioavailability Data
Trimethoprim (1 x 800 mg sulfamethoxazole / 160 mg trimethoprim) Geometric Mean Arithmetic Mean (CV %) | ||||
|---|---|---|---|---|
| Parameter | Test1 | Reference2 | % Ratio of Geometric Means | 90% Confidence Interval |
AUCT (mcg·h/mL) | 20.57 20.90 (16.82) | 20.66 21.01 (18.47) | 99.6 | 92.3 - 107.4 |
AUCI (mcg·h/mL) | 23.36 23.81 (18.89) | 23.59 24.09 (21.00) | 99.0 | 91.1 - 107.6 |
Cmax (mcg /mL) | 1.48 1.49 (11.56) | 1.44 1.46 (16.6) | 102.8 | 94.4 - 111.9 |
Tmax3 (h) | 1.50 (0.50 - 6.00) | 1.50 (0.50 - 4.00) | ||
T1/24 (h) | 10.1 (16.62) | 10.34 (15.76) | ||
1 SULFATRIM DS (sulfamethoxazole and trimethoprim) tablets, 800 mg / 160 mg (AA Pharma Inc.)
2 BACTRIM® DS (sulfamethoxazole and trimethoprim) tablets, 800 mg / 160 mg (Hoffmann-La Roche Limited, Canada)
3 Expressed as the median (range) only
4 Expressed as the arithmetic mean (CV%) only
15. Microbiology
Sulfamethoxazole and trimethoprim is bactericidal in vitro against the gram-negative and gram-positive organisms listed in Table 6.
In vitro Activity: Trimethoprim is, in general, more active than sulfamethoxazole against most bacterial species (see Table 4). Notable exceptions to this include Neisseria gonorrhoeae and Pseudomonas aeruginosa (which is, in general, insensitive to these drugs).
Table 4 – Comparison of Activity of Trimethoprim and Sulfamethoxazole In Vitro
| MIC (mcg / mL) | |||||||||||
| Trimethoprim | Sulfamethoxazole | ||||||||||
| Streptococcus pyogenes | 0.4 | 100 (± 25) | |||||||||
| Diplococcus pneumoniae Type II | 1 | 32 (± 16) | |||||||||
| Viridans streptococci | 0.25 | 8 | |||||||||
| Streptococcus faecalis | 0.5 | 100 | |||||||||
| Streptococcus agalactiae | 4 | 50 | |||||||||
| Staphylococcus aureus | 0.2 | 4 | |||||||||
| Erysipelothrix rhusiopathiae | 8 | >100 | |||||||||
Corynebacterium pyogenes Corynebacterium diphtheriae | 0.4 0.4 | >100 >100 | |||||||||
| Clostridium perfringens | 50 | 16 (± 8) | |||||||||
| Mycobacterium tuberculosis | 250 | >1000 | |||||||||
| Nocardia asteroides | 10 | 5 | |||||||||
| Escherichia coli | 0.2 | 8 | |||||||||
| Citrobacter freundii | 0.1 | 3 | |||||||||
| Klebsiella pneumoniae | 0.5 | 16 | |||||||||
| Klebsiella rhinoscleromatis | 0.5 | 10 | |||||||||
| Enterobacter aerogenes | 3 | >100 | |||||||||
| Salmonella typhi | 0.4 | 4 | |||||||||
| Salmonella typhimurium | 0.3 | 10 | |||||||||
| Shigella spp. | 0.4 | 4 | |||||||||
| Vibrio comma | 0.8 | 32 | |||||||||
| Pasteurella septica | 0.1 | 8 | |||||||||
| Haemophilus influenzae | 0.12 | >50 | |||||||||
| Bordetella pertussis | 3 | 100 | |||||||||
| Moraxella lacunata | 4 | 8 (± 2) | |||||||||
| Proteus spp. | 1 | 8 | |||||||||
| Providence B | 1 | 30 | |||||||||
| Pseudomonas aeruginosa | >100 | 25 | |||||||||
| Pseudomonas pseudomallei | 4 | 10 | |||||||||
| Neisseria gonorrhoeae | 12 | 1.6 | |||||||||
| Neisseria meningitidis | 8 | 1.5 | |||||||||
The activities were compared in the Wellcome Nutrient Agar containing 5% lysed horse blood. For Neisseria and Haemophilus spp., the medium was heated at 80°C for 5 minutes and in the case of Mycobacterium tuberculosis, Peizer and Schacter medium was used.
Demonstration of Synergy
By testing trimethoprim and sulfamethoxazole, both separately and in combination, synergy can be demonstrated in vitro. Synergy is indicated by one or all of the following:
- 1. by a reduction in the MIC of each drug when the drugs are used in combination
- 2. by an increase in the size of the zone of inhibition around the combination disc; and
- 3. by an increase in bactericidal activity when the drugs are used in combination
The reduction in the MIC varies with the ratio of the drugs present and it has been demonstrated that the optimum ratio, as measured by maximum reduction in the MIC's of both drugs, is that in which the drugs are present in proportions corresponding to their respective MIC when acting singly. It should be emphasized, however, that potentiation occurs over a wide range of ratios. With an excess of one of the drugs, the proportion of the other drug may be markedly reduced below that of the optimum ratio, yet still produce a synergistic effect.
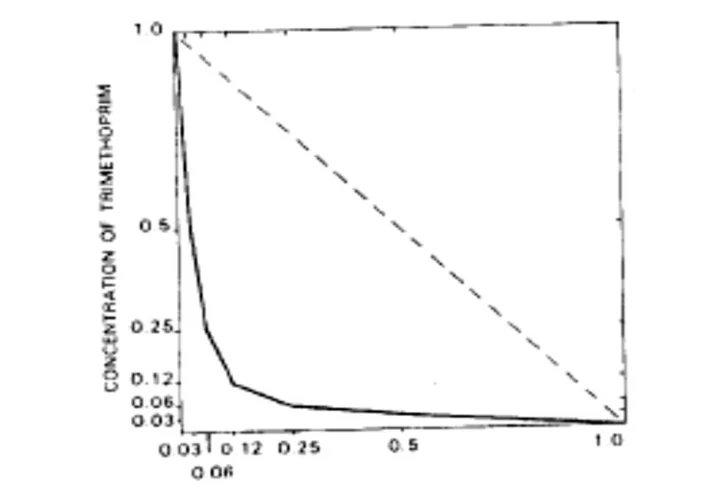
Figure 2 - Isobologram showing the synergy existing between trimethoprim and sulfamethoxazole. Concentrations required to produce 50% inhibition of bacterial growth.
Because of the wide variation in sensitivities of organisms to trimethoprim and sulfamethoxazole, the optimum ratio is also variable and could be different for each organism. Since, in general, trimethoprim is about 20 to 100 times more active than sulfamethoxazole, when examining strains for enhanced susceptibility to the combination investigators have generally preferred to use a fixed ratio, choosing one near the modal optimum. The 1:20 ratio is used most frequently, and examples of the increase in activity are shown in Table 5.
Table 5 – Effect on MIC of Combining 1 Part of Trimethoprim with 20 Parts of Sulfamethoxazole
| Organism | MIC mcg / mL | ||||||||
| Sulfamethoxazole | Trimethoprim | ||||||||
| Alone | Mixture | Alone | Mixture | ||||||
| Streptococcus pyogenes | >100 | 1.0 | 1.0 | 0.050 | |||||
| Diplococcus pneumoniae | 30 | 2.0 | 2.0 | 0.100 | |||||
| Staphylococcus aureus | 3 | 0.3 | 1.0 | 0.015 | |||||
| Haemophilus influenzae | 10 | 0.3 | 1.0 | 0.015 | |||||
| Bordetella pertussis | 50 | 4.0 | 3.0 | 0.200 | |||||
| Klebsiella pneumoniae | >100 | 4.0 | 1.0 | 0.200 | |||||
| Klebsiella aerogenes | >100 | 4.0 | 1.0 | 0.200 | |||||
| Escherichia coli | 3 | 1.0 | 0.3 | 0.050 | |||||
| Salmonella typhimurium | 10 | 1.0 | 0.3 | 0.050 | |||||
| Shigella sonnei | 10 | 1.0 | 0.3 | 0.050 | |||||
| Proteus vulgaris | 30 | 3.0 | 3.0 | 0.150 | |||||
| Neisseria gonorrhoeae | 27 | 1.0 | 14.4 | 0.540 | |||||
Table 6 shows the consolidated reported incidence of sensitivity of 49 165 strains of 40 species to trimethoprim plus sulfamethoxazole from 28 studies. A standard sensitivity disc containing 1.25 mcg trimethoprim and 23.75 mcg sulfamethoxazole was used in each study, but the medium varied.
Table 6 – Incidence of Sensitivity to Trimethoprim + Sulfamethoxazole
| Species | Total No. of Strains | Sensitive Strains | ||||||||
| Species | Total No. of Strains | Sensitive Strains | ||||||||
| Total | % | |||||||||
| Total | % | |||||||||
| S. aureus | 4 929 | 4 280 | 86.8 | |||||||
| S. epidermidis | 99 | 83 | 83.8 | |||||||
| D. pneumoniae | 140 | 140 | 100.0 | |||||||
| St. Pyogenes | 757 | 699 | 92.3 | |||||||
| St. viridans | 873 | 803 | 91.9 | |||||||
| Streptococci | 191 | 102 | 53.4 | |||||||
| St. agalactiae | 20 | 20 | 100.0 | |||||||
Enterococci Escherichia coli | 7 394 18 903 | 3 798 16 851 | 51.4 89.1 | |||||||
| Klebsiella | 1 365 | 1 109 | 81.2 | |||||||
| K. pneumoniae | 12 | 12 | 100.0 | |||||||
| Proteus spp. | 3 142 | 2 436 | 77.5 | |||||||
| Pr. vulgaris | 610 | 402 | 65.9 | |||||||
| Pr. mirabilis | 2 730 | 2 337 | 85.6 | |||||||
| Pr. morganii | 183 | 160 | 87.4 | |||||||
| Pr. rettgeri | 498 | 431 | 86.5 | |||||||
| Providence A | 133 | 104 | 78.2 | |||||||
| Klebs.-Enterobacter | 670 | 458 | 68.4 | |||||||
| Kl. edwardsii | 2 | 2 | 100.0 | |||||||
| Enterobacter | 1 344 | 1 169 | 86.9 | |||||||
| Ent. cloacae | 193 | 187 | 96.9 | |||||||
| Salmonella | 594 | 586 | 98.6 | |||||||
| Hafnia | 92 | 82 | 89.1 | |||||||
| Shigella | 226 | 222 | 98.2 | |||||||
| Sh. dysenteriae | 12 | 8 | 66.7 | |||||||
| Ps. aeruginosa | 3 081 | 600 | 19.5 | |||||||
| Ps. pseudomallei | 12 | 6 | 50.0 | |||||||
| Citrobacter | 202 | 184 | 91.1 | |||||||
| Serratia | 28 | 26 | 92.9 | |||||||
| Paracolobactrum | 84 | 59 | 70.2 | |||||||
| Haemophilus influenzae | 284 | 218 | 76.8 | |||||||
| Flavobacterium | 2 | 2 | 100.0 | |||||||
| Achromobacter | 160 | 124 | 77.5 | |||||||
| Arizona sp. | 18 | 10 | 55.6 | |||||||
| Alcaligenes sp. | 150 | 127 | 84.7 | |||||||
| AD group | 4 | 4 | 100.0 | |||||||
| Cory. diphtheriae | 2 | 2 | 100.0 | |||||||
| Acinetobacter | 16 | 15 | 93.7 | |||||||
| Aeromonas | 4 | 4 | 100.0 | |||||||
| Neisseria Meningitidis | 6 | 6 | 100.0 | |||||||
| Neisseria gonorrhoeae | 32 | 31 | 97.0 | |||||||
The resistance of Bacteroides spp. and Lactobacilli is of special interest, for they comprise the major portion of the flora of the gut. Trimethoprim plus sulfamethoxazole given daily for 10 days to 12 adult volunteers, eliminated all members of the Enterobacteriaceae family from the feces but did not affect either of the former bacterial groups. This lack of effect of these major groups probably accounts for the infrequent occurrence of intestinal upsets during therapy with sulfamethoxazole and trimethoprim.
Trimethoprim and Sulfonamide-Resistant Strains
The theoretical basis for the synergistic effect of sulfamethoxazole and trimethoprim is that sulfamethoxazole reduces the amount of dihydrofolate synthesized by the infecting organism (usually causing bacteriostasis), and an additional small amount of trimethoprim produces a complete block in the conversion of the folate to its active form (usually causing bacterial death).
When examined by conventional susceptibility methods, an organism is regarded as resistant to sulfonamides when its macroscopic growth is not affected. "Resistance" by this definition does not necessarily mean that the sulfonamide has not reduced the folate biosynthesis of the organism. There is indirect enzymatic evidence that the dihydrofolate content of such sulfonamide-resistant strains is, in fact, reduced in the presence of sulfonamides, although not to the same extent as that of sulfonamide-sensitive strains. Therefore, in the presence of sulfamethoxazole, the effect of trimethoprim on these sulfonamide-resistant strains should be increased because the amount of substrate against which the trimethoprim competes is reduced. Streptococcus faecalis is often regarded as being indifferent to the presence of sulfonamides, yet the susceptibility of this organism (and of sulfonamide-resistant strains of Escherichia coli) can be shown to be enhanced markedly with the addition of trimethoprim. Perhaps even more convincing evidence can be obtained by the diffusion method.
Although sulfonamide sensitivity discs produce no zones of inhibition with Streptococcus faecalis, discs containing 23.75 mcg sulfamethoxazole plus 1.25 mcg trimethoprim produce larger zones of inhibited growth of Streptococcus faecalis than do discs containing 1.25 mcg trimethoprim. The difference in size is abolished when para-aminobenzoic acid is present.
Reversal of Trimethoprim Activity
Trimethoprim acts by interfering with the conversion of dihydrofolic acid to tetrahydrofolic acid. Therefore, the presence of an exogenous source of the latter should, theoretically, diminish or even abolish the antibacterial activity of sulfamethoxazole and trimethoprim in the host.
In vitro, 1 mcg/mL folinic acid affects only the sensitivities of Streptococcus faecalis, an organism known to utilize exogenous folates. In vivo, when administered subcutaneously to mice infected with Diplococcus pneumoniae, Streptococcus pyogenes, Escherichia coli, Proteus vulgaris, Salmonella schottmuelleri and Salmonella typhimurium, folinic acid does not affect the ability of trimethoprim to potentiate the antibacterial activity of sulfamethoxazole.
The in vitro interference with the action of trimethoprim and the sulfonamides by thymidine also raises the question of whether thymidine could affect in vivo activity. Experimental studies in the hamster indicate that thymidine is degraded rapidly in vivo. In experiments in mice where large doses of the nucleoside were given intraperitoneally, it did not interfere with the protection afforded by trimethoprim and sulfamethoxazole against Proteus vulgaris.
Resistance Development
During the serial passage in the presence of trimethoprim, little change in sensitivity occurs with light inocula; however, resistance develops rapidly with heavy inocula. With sulfonamide-sensitive strains, the emergence of these mutants is markedly delayed by the presence of sulfamethoxazole. The delaying effect of the sulfonamide depends, however, on the degree of sulfonamide resistance and is minimal with highly resistant strains.
Recently, R factors conferring high degrees of trimethoprim resistance have been identified in members of the Enterobacteriaceae family isolated from man and animals. A factor conferring high trimethoprim and sulfonamide resistance was detected in a strain of Escherichia coli and in a strain of Klebsiella aerogenes. Both strains were isolated from infected urine of human patients.
16. Non-Clinical Toxicology
General Toxicology
Acute Studies:
Acute toxicity studies in rats of the separate components and of trimethoprim and sulfamethoxazole combined in a ratio of 1:5 demonstrated the following LD50 values:
| Sulfamethoxazole | Trimethoprim | 1:5 | |
| Rats (Adult) oral | 2000 mg / kg | 1500 mg / kg | 6500 mg / kg |
| Rats (Neonates) oral | 1360 mg / kg | 195 mg / kg | 1160 mg / kg |
Subacute Studies:
Daily dosages of 33, 100, and 300 mg / kg of trimethoprim and 133, 400, and 1200 mg / kg of sulfamethoxazole were given to young, sexually immature rhesus monkeys for one month. The compounds were also given in combination; the lower doses of each being combined, and similarly the higher ones. Effects on weight gain were seen. Loss in weight was noted with high and medium dosage groups with the combined drugs. Changes were induced in hemopoiesis which were consistent with trimethoprim action in interfering with dihydrofolate reductase activity. Also high doses of the sulfonamide produce hypoplastic hemopoietic changes. Half the animals on high dose levels showed increased blood urea concentrations.
A similar study in rats produced similar results. In addition, some changes associated with the sulfonamide were noted in the thyroid and in the pituitary, such as increased weight and epithelial changes. Fatty changes were also seen in the liver of monkeys and rats on the medium and high dose levels.
Chronic Studies:
Six Months:
Toxicity studies of six months duration were conducted in rats and monkeys with a combination of trimethoprim and sulfamethoxazole (1:2 ratio) with total daily oral doses ranging between 99 and 900 mg / kg.
Doses of 99 mg / kg daily for six months were well-tolerated in both species with minimal signs of toxicity; 300 mg / kg was well-tolerated by monkeys, but in rats impaired growth was seen and 2 of the 10 animals in this dosage group died. With 900 mg / kg, marked effects on growth and on survival occurred in both species.
Histopathological examinations were made on more than 20 different tissues from each species; these showed depression of hematopoiesis in both species in the 300 and 900 mg / kg dosage groups and minor changes with 99 mg / kg. These bone marrow changes were related to trimethoprim's interference with dihydrofolate reductase activity. Other tissue changes attributed to drug action seen in the rat, but not in the monkey, were thyroid hyperplasia and pituitary cytological effects, both associated with the sulfonamide moiety.
12 to 14 Months:
Oral toxicity studies with trimethoprim and sulfamethoxazole, singly or in a 1:5 combination, were conducted in the monkey and in the rat. For the monkey, dose levels ranging from 10 + 50 to 60 + 300 mg / kg six days per week were employed for a period of 52 weeks; for the rat, dose levels ranging from 5 + 25 to 120 + 600 mg / kg per day were employed for a duration of 60 weeks.
In the monkey, the 1:5 combination did not produce any significant compound-related effects, except for a slight reduction in weight gain in the 60 + 300 mg / kg dose group.
In the rat study, thyroid hyperplasia of a dose-related severity was seen after 13 weeks in all animals receiving sulfamethoxazole. This hyperplasia progressed to nodularity or adenoma formation in some rats after 52 weeks at doses as low as 50 mg / kg per day, and to local vascular invasion and lung metastases after 60 weeks at doses as low as 150 mg / kg per day. Pituitary changes (large pale cells, often vacuolated), considered to be secondary to the thyroid change, were found in a few rats in all the sulfamethoxazole treated groups.
The phenomenon of thyroid hyperplasia in rats has been produced in this species by a number of sulfonamides and antithyroid drugs. The thyroid hyperplasia which occurs under the influence of these drugs is considered to be compensatory to the failure of thyroid hormone synthesis; it has been stated that this hyperplasia can be prevented or reversed by thyroid hormone. The progression of thyroid hyperplasia to nodule or adenoma formation is an observation in rats which has been reported previously in the literature on the antithyroid drugs, thiouracil and thiourea. It is considered that in these studies the production of thyroid tumours was due, not to any direct carcinogenic action of the drugs, but rather to the excessive and prolonged stimulation of the thyroid epithelium by the thyrotropic secretion of the pituitary.
Other changes associated with sulfamethoxazole treatment in our animal studies were: a dose-related increased alkaline phosphatase, a dose-related reduction in mean body weight gain, slight depression of hematopoiesis, testicular atrophy, focal renal calcification, and slightly increased fat vacuolation of the liver and kidney.
Reproductive and Developmental Toxicology
A three-phase investigation, comprised of a fertility and general reproductive performance study and a perinatal and postnatal study in the rat, and teratology studies in the rat and rabbit, were conducted with an orally administered 1:5 combination of trimethoprim to sulfamethoxazole. The dose levels investigated, singly or combined, were 70 + 350, 30 + 150, 15 + 75, 0 + 350, 0 + 150, 0 + 75, and 14 + 0 or 70 + 0 mg / kg.
Some drug-related effects noted in the investigation were: a reduced body weight gain by eight weeks in males in the Fertility and General Reproductive Performance Study at dose levels of 150 or 350 mg / kg of sulfamethoxazole, alone or in combination, and an increased incidence of maternal mortality in the rabbit teratology study at the same dose levels. In one of the 18 litters of the high combination group, four of the eight pups were abnormal. Two had bone malformations and two had curled tails, missing or small kidneys, absence of eyelid and one also had misshapen lateral ventricles of the brain. The instances of small, underdeveloped kidneys were such as to raise a question of dose relationships. In the teratogenicity study in rats, instances of small, underdeveloped kidneys were seen: in control group - 0; in combination groups (420 mg / kg dose) - 6 (8.5%), (180 mg / kg dose) - 3 (4.7%), (90 mg / kg dose) - 2 (3.2%). Other malformations noted in a group receiving 420 mg/kg, were one instance of incomplete nasal septum and two fetuses with abnormally large openings in the lateral ventricles. Fertility and general reproductive performance, and early and late fetal development were not affected by the dose regimen employed.
Fertility:
In these studies, the animals were dosed per os with a 1:5 mixture of trimethoprim to sulfamethoxazole daily from 60 days before mating until the end of weaning.
In the rat, at 600 mg / kg there was a slight, non-significant lowering of the pregnancy rate when compared with controls. The number of live progeny per litter at birth and at weaning was less than in controls. A slight treatment-related disturbance of estrus and of sperm count was also noted.
With 200 mg / kg the pregnancy rate was slightly lower than in controls, but the other effects seen with the higher dose were not noted.
In the rabbit, daily oral doses of 600 mg / kg produced vomiting, even with divided doses, and was therefore abandoned. Two hundred mg / kg did not have a significant effect on the pregnancy rate, on the number of live births per litter, or on the mean weight of progeny at birth or at weaning.
Teratogenicity:
In these studies, rats and rabbits were dosed by stomach tube daily from days 8 to 16 of pregnancy, or on a single day of pregnancy (rat only). Trimethoprim and sulfamethoxazole were used alone, in a 1:4 combination, and in a 1:2 combination.
For the rat, dosing with 500 mg / kg of trimethoprim on any single day of gestation between days 8 to 16 had no effect on the dams or their fetuses. A single dose of 2000 mg / kg of trimethoprim was lethal to most fetuses when given on the eighth or ninth day, and it produced a very high incidence of malformations when given on days 10, 11 or 12. However, the incidence of these malformations dropped off precipitately when dosing was on the 13th day or later.
The most common abnormality seen with either compound in the rat, when dosing was daily on days 8 to 16 of pregnancy, was cleft palate which occurred with 200 mg / kg of trimethoprim alone and with 640 mg / kg of sulfamethoxazole alone. Higher doses of trimethoprim produced bony defects and exencephaly, related to its action in interfering with dihydrofolate reductase activity. The abnormalities could be prevented by the administration of folinic acid subcutaneously. No fetal abnormalities were found at daily doses of 160 mg / kg or less of trimethoprim, or 512 mg / kg or less of sulfamethoxazole. Using compounds in a 1:4 trimethoprim/sulfamethoxazole combination, fetal malformations appeared at between 128 mg / kg and 160 mg / kg of trimethoprim and 512 mg/kg and 640 mg / kg of sulfamethoxazole. There appeared to be a distinct synergism with the 1 to 2 mixture.
In rabbits given the drug daily during organogenesis (days 8 to 16), no teratogenic effect was revealed with the 1:4 mixture or its components. While no important effect on the incidence of dead fetuses was noted with daily doses of 125 mg / kg of trimethoprim, 500 mg / kg or less of sulfamethoxazole, or with 312.5 mg / kg of the combination, the incidence of fetuses dying before full term was higher than for controls in the groups given trimethoprim except at the 62.5 mg / kg dose. Pregnant does tolerated the combination better than sulfamethoxazole alone.
17. Supporting Product Monographs
- 1. BACTRIM (sulfamethoxazole and trimethoprim tablets, 400 mg sulfamethoxazole and 80 mg trimethoprim), BACTRIM DS (sulfamethoxazole and trimethoprim tablets, 800 mg sulfamethoxazole and 160 mg trimethoprim), BACTRIM PAEDIATRIC SUSPENSION (sulfamethoxazole and trimethoprim suspension, 200 mg / 5 mL sulfamethoxazole and 40 mg / 5 mL trimethoprim), and BACTRIM INJECTION (sulfamethoxazole and trimethoprim solution, 80 mg / mL sulfamethoxazole and 16 mg / mL trimethoprim), product monograph, Hoffmann-La Roche Limited. (1998-07-30)
- 2. SEPTRA® Injection (sulfamethoxazole and trimethoprim sterile solution, 80 mg / mL sulfamethoxazole and 16 mg / mL trimethoprim) and SEPTRA® PEDIATRIC ORAL SUSPENSION (sulfamethoxazole and trimethoprim oral suspension, 40 mg / mL sulfamethoxazole and 8 mg / mL trimethoprim, control 306093, product monograph, Aspen Pharmacare Canada Inc. (2026-07-03)