


Product Monograph - Tamiflu
Recent Major Label Changes
| None at time of the most recent authorization |
|---|
Table of Contents
Certain sections or subsections that are not applicable at the time of the preparation of the most recent authorized product monograph are not listed.
Recent Major Label Changes .................................................................................................. 2
Table of Contents................................................................................................................... 2
Part 1: Healthcare Professional Information........................................................................... 4
- 1.
Indications ...................................................................................................................... 4
1.1. Pediatrics ............................................................................................................ 5
1.2. Geriatrics............................................................................................................. 5
- 2. Contraindications ............................................................................................................ 5
- 4.
Dosage and Administration ............................................................................................. 5
4.1. Dosing Considerations ......................................................................................... 5
4.2. Recommended Dose and Dosage Adjustment....................................................... 5
4.3. Reconstitution ..................................................................................................... 8
4.4. Administration................................................................................................... 11
4.5. Missed Dose ...................................................................................................... 11
- 5. Overdose ...................................................................................................................... 11
- 6. Dosage Forms, Strengths, Composition, and Packaging ................................................. 12
- 7.
Warnings and Precautions............................................................................................. 13
General ......................................................................................................................... 13
Endocrine and Metabolism ............................................................................................ 14
Hepatic/Biliary/Pancreatic ............................................................................................. 14
Psychiatric ..................................................................................................................... 14
Renal............................................................................................................................. 14
Sensitivity/Resistance .................................................................................................... 14
Skin ............................................................................................................................... 15
7.1. Special Populations ............................................................................................ 15
7.1.1. Pregnancy .................................................................................................. 15
7.1.2. Breastfeeding............................................................................................. 15
7.1.3. Pediatrics ................................................................................................... 16
7.1.4. Geriatrics ................................................................................................... 16
- 8.
Adverse Reactions......................................................................................................... 16
8.1. Adverse Reaction Overview................................................................................ 16
8.2. Clinical Trial Adverse Reactions .......................................................................... 16
8.2.1. Clinical Trial Adverse Reactions – Pediatrics ................................................ 19
8.3. Less Common Clinical Trial Adverse Reactions .................................................... 21
8.4. Abnormal Laboratory Findings: Hematologic, Clinical Chemistry, and Other Quantitative Data .......................................................................................................... 21
8.5. Post-Market Adverse Reactions.......................................................................... 21
- 9.
Drug Interactions .......................................................................................................... 21
9.2. Drug Interactions Overview................................................................................ 21
9.3. Drug-Behaviour Interactions .............................................................................. 22
9.4. Drug-Drug Interactions ...................................................................................... 22
9.5. Drug-Food Interactions ...................................................................................... 22
9.6. Drug-Herb Interactions ...................................................................................... 22
9.7. Drug-Laboratory Test Interactions ...................................................................... 22
- 10.
Clinical Pharmacology ................................................................................................... 23
10.1. Mechanism of Action ......................................................................................... 23
10.2. Pharmacodynamics............................................................................................ 24
10.3. Pharmacokinetics .............................................................................................. 24
- 11. Storage, Stability, and Disposal ..................................................................................... 25
Part 2: Scientific Information ............................................................................................... 27
- 13. Pharmaceutical Information.......................................................................................... 27
- 14.
Clinical Trials ................................................................................................................. 27
14.1. Clinical Trials by Indication ................................................................................. 27
- 15. Microbiology................................................................................................................. 31
- 16. Non-Clinical Toxicology ................................................................................................. 33
Patient Medication Information........................................................................................... 35
Patient Medication Information........................................................................................... 40
Part 1: Healthcare Professional Information
1. Indications
TAMIFLU (oseltamivir phosphate, capsules and powder for oral suspension) is indicated for:
The treatment of uncomplicated acute illness due to influenza infection in adults and adolescents (≥ 13 years) who have been symptomatic for no more than 2 days.
The treatment indication is based on two Phase III clinical studies of naturally occurring influenza in adults in which the predominant infection was influenza A (95%) and a limited number with influenza B (3%) and influenza of unknown type (2%), reflecting the distribution of these strains in the community. The indication is also supported by influenza A and B challenge studies. No data are available to support the safety and efficacy of TAMIFLU in adult patients who commenced treatment after 40 hours of onset of symptoms.
The treatment of uncomplicated acute illness due to influenza in pediatric patients 1 year and older who have been symptomatic for no more than 2 days.
The pediatric indication is based on one Phase III clinical study of naturally occurring influenza in pediatric patients aged 1 to 12 years in which 67% of influenza infected patients were infected with influenza A and 33% with influenza B.
TAMIFLU, when taken as recommended for the treatment of influenza, alleviates the symptoms and reduces their duration (see 14 Clinical Trials).
Prevention/Prophylaxis of Influenza
The decision to administer TAMIFLU for prophylaxis to close contacts should be based on the knowledge that influenza is circulating in the area and the index case demonstrates characteristic symptoms of influenza. TAMIFLU is not effective in providing prophylaxis for respiratory infections other than influenza, therefore a proper diagnosis of the index case is important.
TAMIFLU is not a substitute for influenza vaccination. Vaccination is the preferred method of prophylactic prevention against influenza. The use of TAMIFLU should not affect the evaluation of individuals for annual influenza vaccination, in accordance to “Health Canada. An Advisory Committee Statement on Influenza Vaccination for the Current Year/Season.”
The use of antivirals for the treatment and prevention of influenza should be determined on the basis of official recommendations taking into consideration variability of epidemiology and the impact of the disease in different geographical areas and patient populations.
TAMIFLU (oseltamivir phosphate, capsules and powder for oral suspension) is indicated for:
The prevention of influenza illness in adults and adolescents 13 years and older following close contact with an infected individual (the index case).
The prevention indication is based on a Phase III clinical study programme consisting of 4 Phase III clinical trials.
The prevention of influenza illness in pediatric patients 1 year and older following close contact with an infected individual (the index case).
This indication is based on a sub-study of pediatric patients in a Phase III clinical trial.
1.1. Pediatrics
Pediatrics (< 1 year of age): The efficacy of TAMIFLU in infants younger than 1 year of age have not been established (see 7 Warnings and Precautions, 7.1.3 Pediatrics and 14 Clinical Trials); therefore, Health Canada has not authorized an indication for pediatric use.
1.2. Geriatrics
Geriatrics (≥ 65 years of age): Efficacy of TAMIFLU in the treatment of elderly patients has not been evaluated. Safety data in 372 elderly patients (≥ 65 years old) showed no overall difference between these subjects and younger adults. Based on drug exposure and tolerability, dosage adjustments are not anticipated for elderly patients (see 7 Warnings and Precautions, 7.1.4 Geriatrics and 10 Clinical Pharmacology, 10.3 Pharmacokinetics, Special Populations and Conditions, Geriatrics).
2. Contraindications
- TAMIFLU (oseltamivir phosphate) is contraindicated in patients who are hypersensitive to this drug or to any ingredient in the formulation, including any non-medicinal ingredient, or component of the container. For a complete listing, see 6 Dosage Forms, Strengths, Composition, and Packaging.
4. Dosage and Administration
4.1. Dosing Considerations
- Hepatic Impairment: The safety, efficacy and pharmacokinetics in patients with severe hepatic impairment have not been studied. No studies have been carried out in pediatric patients with hepatic impairment.
- Infants: The efficacy of TAMIFLU (oseltamivir phosphate) in infants younger than 1 year of age has not been established. TAMIFLU should not be used in children under 1 year of age (see 16 Non-Clinical Toxicology, General Toxicology, Multiple Dose Toxicity).
- For information on renal impairment and elderly patients, see 4.2 Recommended Dose and Dosage Adjustment, Dosage Adjustment.
4.2. Recommended Dose and Dosage Adjustment
Recommended Dose – Treatment of Influenza
Treatment should begin no more than two days after the onset of symptoms of influenza.
Adults and Adolescents (≥ 13 years): The recommended oral dose of TAMIFLU capsules for the treatment of influenza in adults and adolescents 13 years and older is 75 mg twice daily, for 5 days.
Pediatrics (1 to 12 years): The recommended oral dose of TAMIFLU oral suspension for pediatric patients 1 year and older is shown in the table below. TAMIFLU oral suspension may also be used by adult patients who cannot swallow a capsule. If TAMIFLU oral suspension is not available, TAMIFLU capsules may be opened and mixed with sweetened liquids such as regular or sugar-free chocolate syrup. For children old enough to safely swallow capsules, the 30 and 45 mg capsules can also be taken as outlined in the table below.
| Body Weight in kg | Body Weight in lbs | Recommended Dose for 5 Days | Amount of Oral Suspension (6 mg/mL) |
| ≤ 15 kg | ≤ 33 lbs | 30 mg twice daily | 5.0 mL twice daily |
| > 15 kg to 23 kg | > 33 lbs to 51 lbs | 45 mg twice daily | 7.5 mL twice daily |
| > 23 kg to 40 kg | > 51 lbs to 88 lbs | 60 mg twice daily | 10.0 mL twice daily |
| > 40 kg | > 88 lbs | 75 mg twice daily | 12.5 mL twice daily |
Use appropriate oral dosing dispenser for volume dispensed with the oral suspension; the 75 mg dose can be measured using a combination of 30 mg and 45 mg. In the event that the dispenser provided is lost or damaged, another dosing dispenser may be used to deliver the volumes.
Recommended Dose – Prevention of Influenza
Therapy should begin within 2 days of exposure after the onset of symptoms in the index case and continue for at least ten days. Viral shedding may continue for up to 14 days in children and elderly after the onset of influenza illness. Therefore, if the index case is a child or an elderly person, therapy with TAMIFLU for prevention may continue for up to 14 days.
Patients should be instructed to complete the entire course of therapy.
Adults and adolescents (≥ 13 years): The recommended oral dose of TAMIFLU for prevention of influenza following close contact with an infected individual (the index case) is 75 mg once daily.
Safety has been demonstrated for up to 12 weeks in immunocompromised patients.
Pediatrics (1 to 12 years): The recommended dose of TAMIFLU oral suspension for prevention in pediatric patients 1 year and older is shown in the table below. TAMIFLU oral suspension may also be used by adult patients who cannot swallow a capsule. If TAMIFLU oral suspension is not available, TAMIFLU capsules may be opened and mixed with sweetened liquids such as regular or sugar-free chocolate syrup. For children old enough to safely swallow capsules, the 30 and 45 mg capsules can also be taken as outlined in the table below.
| Body Weight in kg | Body Weight in lbs | Recommended Dose for at least 10 Days | Amount of Oral Suspension (6 mg/mL) |
| ≤ 15 kg | ≤ 33 lbs | 30 mg once daily | 5.0 mL once daily |
| > 15 kg to 23 kg | > 33 lbs to 51 lbs | 45 mg once daily | 7.5 mL once daily |
| > 23 kg to 40 kg | > 51 lbs to 88 lbs | 60 mg once daily | 10.0 mL once daily |
| > 40 kg | > 88 lbs | 75 mg once daily | 12.5 mL once daily |
Use appropriate oral dosing dispenser for volume dispensed with the oral suspension; the 75 mg dose can be measured using a combination of 30 mg and 45 mg. In the event that the dispenser provided is lost or damaged, another dosing dispenser may be used to deliver the volumes.
Dosing for Pharmacy-Compounded Suspension
Table 1: Dosing Chart for Pharmacy-Compounded Suspension from TAMIFLU Capsules 75 mg
| Body Weight (kg) | Body Weight (lbs) | Dose (mg) | Volume per Dose 6 mg/mL | Treatment Dose (for 5 days) | Prophylaxis Dose (for 10 days) |
| ≤ 15 kg | ≤ 33 lbs | 30 mg | 5 mL | 5 mL two times a day | 5 mL once daily |
| 16 to 23 kg | 34 to 51 lbs | 45 mg | 7.5 mL | 7.5 mL two times a day | 7.5 mL once daily |
| 24 to 40 kg | 52 to 88 lbs | 60 mg | 10 mL | 10 mL two times a day | 10 mL once daily |
| ≥ 41 kg | ≥ 89 lbs | 75 mg | 12.5 mL | 12.5 mL two times a day | 12.5 mL once daily |
Note: 1 teaspoon = 5 mL
Dosage Adjustment
Hepatic Impairment: No dose adjustment is required in adult patients with mild or moderate hepatic impairment (see 10 Clinical Pharmacology, 10.3 Pharmacokinetics, Special Populations and Conditions, Hepatic Insufficiency).
Renal Impairment: No dose adjustment is necessary for patients with creatinine clearance above 60 mL/min. Dosage adjustments for adult patients with creatinine clearance ≤ 60 mL/min are as indicated below. Note that the dosage adjustments are based primarily on population pharmacokinetic modeling data. Clinical safety and efficacy studies at these doses have not been performed.
Treatment of Influenza: In adult patients with a creatinine clearance of > 30-60 mL/min, it is recommended that the dose be reduced to 30 mg of TAMIFLU twice daily for 5 days.
In adult patients with a creatinine clearance of 10-30 mL/min, it is recommended that the dose be reduced to 30 mg of TAMIFLU once daily for 5 days.
Treatment of Influenza for patients undergoing routine hemodialysis: In adult patients, an initial dose of 30 mg of TAMIFLU can be administered prior to the start of dialysis if influenza symptoms develop during the 48 hours between dialysis sessions. To maintain plasma concentrations at a therapeutic level, a dose of 30 mg of TAMIFLU should be administered after every hemodialysis session, over a period of 5 days.
For adult patients on continuous ambulatory peritoneal dialysis (CAPD), a single 30 mg dose of TAMIFLU administered prior to the start of dialysis is recommended for treatment.
Prevention of influenza: In adult patients with a creatinine clearance of > 30-60 mL/min, it is recommended that the dose be reduced to 30 mg of TAMIFLU once daily for 10-14 days.
In adult patients with a creatinine clearance of 10-30 mL/min, it is recommended that the dose be reduced to 30 mg of TAMIFLU every other day for a period of 10-14 days.
Prevention of Influenza for patients undergoing routine hemodialysis: In adult patients, an initial dose of 30 mg of TAMIFLU can be administered prior to the start of dialysis. To maintain plasma concentrations at a therapeutic level, a dose of 30 mg should be administered after every alternate hemodialysis session for a period of 10-14 days.
For adult patients on peritoneal dialysis, an initial dose of 30 mg of TAMIFLU administered prior to the start of dialysis followed by further 30 mg doses administered every 7 days, for a period of 10-14 days, is recommended for prophylaxis.
Note that the pharmacokinetics of oseltamivir have not been studied in patients with end-stage renal disease (i.e., creatinine clearance of < 10 mL/min) not undergoing dialysis. Hence, dosing recommendation cannot be provided for this group.
Geriatrics: No dose adjustment is required for elderly patients with normal renal function (see 7 Warnings and Precautions, 7.1 Special Populations, 7.1.4 Geriatrics).
4.3. Reconstitution
Reconstitution of Oral Suspension:
It is recommended that TAMIFLU powder for oral suspension be reconstituted by the pharmacist prior to dispensing to the patient.
- 1. Tap the closed bottle several times to loosen the powder.
- 2. Measure 55 mL of water in a graduated cylinder*.
- 3. Add the total amount of water for reconstitution to the bottle and shake the closed bottle well for 15 seconds. (The bottle containing 390 mg oseltamivir will contain 65 mL of suspension at a final concentration of 6 mg/mL of oseltamivir (as oseltamivir phosphate) when reconstituted.)
- 4. Remove the child-resistant cap and push bottle adapter into neck of bottle.
- 5. Close bottle with child-resistant cap tightly. This will assure the proper seating of the bottle adapter in the bottle and child-resistant status of the cap.
*Please ensure the overcap provided is not dispensed to the patient if TAMIFLU powder for oral suspension is reconstituted by the pharmacist.
Dispense with patient information leaflet and oral dispenser. It is recommended to write the date of expiration of the reconstituted suspension on the bottle label. (The shelf life of the reconstituted suspension is 10 days if stored at room temperature (not above 25°C) or 17 days if stored in a refrigerator (2-8°C)).
Emergency Compounding of an Oral Suspension from TAMIFLU Capsules (Final Concentration 6 mg/mL):
The following directions are provided for use only during emergency situations. These directions are not intended to be used if the Health Canada-approved, commercially manufactured TAMIFLU for Oral Suspension is readily available from wholesalers or the manufacturer.
Compounding an oral suspension with this procedure will provide one patient with enough medication for a 5-day course of treatment or a 10-day course of prophylaxis.
Commercially manufactured TAMIFLU for Oral Suspension (6 mg/mL) is the preferred product for pediatric and adult patients who have difficulty swallowing capsules or where lower doses are needed. In the event that TAMIFLU for Oral Suspension is not available, the pharmacist may compound a suspension (6 mg/mL) from TAMIFLU (oseltamivir phosphate) Capsules 75 mg using one of the following vehicles: Cherry Syrup (Humco®), Ora-Sweet® SF (sugar-free) (Paddock Laboratories), simple syrup OR purified water containing 0.05% w/v sodium benzoate added as preservative. Other vehicles have not been studied. This compounded suspension should not be used for convenience or when the Health Canada-approved TAMIFLU for Oral Suspension is commercially available.
First, calculate the Total Volume of an oral suspension needed to be compounded and dispensed for each patient. The Total Volume required is determined by the weight of each patient. Refer to Table 2.
Table 2: Volume of an Oral Suspension (6 mg/mL) needed to be Compounded Based upon the Patient’s Weight
| Body Weight (kg) | Body Weight (lbs) | Total Volume to Compound per patient (mL) |
| ≤ 15 kg | ≤ 33 lbs | 75 mL |
| 16 to 23 kg | 34 to 51 lbs | 100 mL |
| 24 to 40 kg | 52 to 88 lbs | 125 mL |
| ≥ 41 kg | ≥ 89 lbs | 150 mL |
Second, determine the number of capsules and the amount of vehicle (Cherry Syrup (Humco®), Ora-Sweet SF, simple syrup OR purified water containing 0.05% w/v sodium benzoate added as preservative) that are needed to prepare the Total Volume (calculated from Table 2: 75 mL, 100 mL, 125 mL, or 150 mL) of compounded oral suspension (6 mg/mL). Refer to Table 3.
Table 3: Number of TAMIFLU 75 mg Capsules and Amount of Vehicle (Cherry Syrup (Humco®), Ora-Sweet SF, simple syrup OR purified water containing 0.05% w/v sodium benzoate added as preservative) needed to Prepare the Total Volume of a Compounded Oral Suspension (6 mg/mL)
* Includes overage to ensure all doses can be delivered
| Total Volume of Compounded Oral Suspension needed to be Prepared | 75 mL | 100 mL | 125 mL | 150 mL |
| Required number of TAMIFLU 75 mg Capsules* | 6 capsules (450 mg oseltamivir) | 8 capsules (600 mg oseltamivir) | 10 capsules (750 mg oseltamivir) | 12 capsules (900 mg oseltamivir) |
| Required volume of water | 5 mL | 7 mL | 8 mL | 10 mL |
Required volume of vehicle Cherry Syrup (Humco®) OR simple syrup OR Ora-Sweet SF (Paddock Laboratories) | 69 mL | 91 mL | 115 mL | 137 mL |
* Includes overage to ensure all doses can be delivered
Third, follow the procedure below for compounding the oral suspension (6 mg/mL) from TAMIFLU Capsules 75 mg:
- 1. If using Cherry Syrup (Humco®), Ora-Sweet SF, or simple syrup as a vehicle, place the specified amount of water into an amber glass or amber polyethyleneterephthalate (PET) bottle, see Table 3. [Alternatively, if using purified water containing 0.05% w/v sodium benzoate (added as preservative) as a vehicle, start at Step 2.]
- 2. Carefully separate the capsule body and cap and transfer the contents of the required number of TAMIFLU 75 mg capsules into a clean mortar.
- 3. Triturate the granules to a fine powder.
- 4. Add one-third (1/3) of the specified amount of vehicle and levigate the powder until a uniform suspension is achieved.
- 5. Transfer the suspension to an amber glass or amber PET bottle (if using Cherry Syrup (Humco®), Ora-Sweet SF, or simple syrup as a vehicle, use the same amber glass or amber PET bottle from step 1). A funnel may be used to eliminate any spillage.
- 6. Add another one-third (1/3) of the vehicle to the mortar, rinse the pestle and mortar by a triturating motion and transfer the vehicle into the bottle.
- 7. Repeat the rinsing (Step 6) with the remainder of the vehicle.
- 8. Close the bottle using a child-resistant cap.
- 9. Shake well to completely dissolve the active drug and to ensure homogeneous distribution of the dissolved drug in the resulting suspension. (Note: The active drug, oseltamivir phosphate, readily dissolves in the specified vehicle. The suspension is caused by some of the inert ingredients of TAMIFLU Capsules which are insoluble in the vehicle.)
- 10. Put an ancillary label on the bottle indicating “Shake Gently Before Use”. [This compounded suspension should be gently shaken prior to administration to minimize the tendency for air entrapment.]
- 11. Instruct the parent or guardian that any remaining material following completion of therapy must be discarded by either affixing an ancillary label to the bottle or adding a statement to the pharmacy label instructions.
- 12. Place an appropriate expiration date label according to storage condition (see 11 Storage,
| Total Volume of Compounded Oral Suspension needed to be Prepared | 75 mL | 100 mL | 125 mL | 150 mL |
| Required number of TAMIFLU 75 mg Capsules* | 6 capsules (450 mg oseltamivir) | 8 capsules (600 mg oseltamivir) | 10 capsules (750 mg oseltamivir) | 12 capsules (900 mg oseltamivir) |
| purified water containing 0.05% w/v sodium benzoate added as preservative | 74 mL | 98 mL | 123 mL | 147 mL |
- Stability, and Disposal).
Place a pharmacy label on the bottle that includes the patient’s name, dosing instructions, and drug name and any other required information to be in compliance with all Provincial and Federal Pharmacy Regulations. Refer to Table 1 for the dosing instructions (see 4 Dosage and Administration, 4.2 Recommended Dose and Dosage Adjustment, Dosing for Pharmacy-Compounded Suspension).
Emergency Home Preparation of an Oral Suspension from TAMIFLU Capsules:
If the commercially manufactured TAMIFLU oral suspension (6 mg/mL) is not available and the pharmacy compounded suspension is also not available, TAMIFLU suspension may be prepared at home if directed by the healthcare provider.
When appropriate capsule strengths are available for the dose needed (75 mg, 45 mg and 30 mg), the dose is given by opening the capsule and mixing its contents with no more than one teaspoon of a suitable sweetened food product (e.g. chocolate syrup, cherry syrup, sugar water, dessert toppings). The mixture should be stirred and given entirely to the patient. The mixture must be swallowed immediately after its preparation.
Detailed instructions can be found in the Patient Medication Information for TAMIFLU oseltamivir capsules under “Emergency Home Preparation of an Oral Suspension from TAMIFLU Capsules”.
4.4. Administration
TAMIFLU may be taken with or without food (see 10 Clinical Pharmacology, 10.3 Pharmacokinetics, Absorption). However, taking with food may enhance tolerability in some patients.
Shake the TAMIFLU oral suspension well before each use.
Pharmacy-Compounded Suspension
Consider dispensing the suspension with a graduated oral syringe for measuring small amounts of suspension. If possible, mark or highlight the graduation corresponding to the appropriate dose on the oral syringe for each patient. In the event that the dispenser provided is lost or damaged, another dosing dispenser may be used to deliver the volumes.
For the suspension compounded with purified water containing 0.05% w/v sodium benzoate added as a preservative, the appropriate dose must be withdrawn from the dispensed bottle by the caregiver. Using a separate container, the withdrawn dose must be mixed with an equal amount of sweetened liquid, such as sugar water, chocolate syrup, cherry syrup, dessert toppings (like caramel or fudge sauce) to mask the bitter taste.
4.5. Missed Dose
The missed dose should be taken as soon as remembered, then the regular dosing schedule should be continued. Two doses of TAMIFLU should not be taken at the same time.
5. Overdose
Activated charcoal may be administered to aid in the removal of unabsorbed drug. General supportive measures are recommended.
Reports of overdoses with TAMIFLU have been received from clinical trials and during post-marketing experience. These overdose cases included single or repeated overdose, accidental or intended. The majority of overdose cases were reported in children.
A subset of 114 overdose cases was evaluated in detail, where overdose was defined as receiving more than twice the recommended dose. From the 114 patients, 31% ingested TAMIFLU in an overdose amount ranging from > 2 to < 4 fold the recommended dose (on single or multiple occasions), 49% experienced an overdose between 4 and < 9 fold the recommended dose, and 17% experienced a 9-fold or higher overdose. In the remaining 3% of patients, enough information was not provided to determine the exact amount of overdose.
The most frequently reported adverse events were gastrointestinal disorders, followed by psychiatric and nervous disorders. In the majority of cases reporting overdose, no adverse events were reported. Adverse events reported following overdose were similar in nature and distribution to those observed with therapeutic doses of TAMIFLU, described in 8 Adverse Reactions.
| For the most recent information in the management of a suspected drug overdose, contact your regional poison control centre or Health Canada’s toll-free number, 1-844 POISON-X (1-844-764-7669). |
|---|
- 6. Dosage Forms, Strengths, Composition, and Packaging
Table 4 – Dosage Forms, Strengths, and Composition
| Route of Administration | Dosage Form / Strength/Composition | Non-medicinal Ingredients |
| Oral | Capsule / 30 mg, 45 mg and 75 mg oseltamivir (as oseltamivir phosphate) | Corn starch, croscarmellose sodium, povidone K30, sodium stearyl fumarate and talc. The 30 mg capsule shell contains gelatin, red iron oxide, titanium dioxide and yellow iron oxide. The 45 mg capsule shell contains black iron oxide, gelatin and titanium dioxide. The 75 mg capsule shell contains black iron oxide, gelatin, red iron oxide, titanium dioxide and yellow iron oxide. Each capsule is printed with blue ink, which includes FD&C Blue No. 2 as a colourant. |
| Oral | Powder for Oral Suspension / 6 mg/mL oseltamivir (as oseltamivir phosphate) when reconstituted | Monosodium citrate, saccharin sodium, sodium benzoate, sorbitol, titanium dioxide, tutti-frutti flavouring and xanthan gum. |
TAMIFLU (oseltamivir phosphate) 30 mg, 45 mg and 75 mg Capsules
TAMIFLU 30 mg capsules are available as light yellow hard gelatin capsules. “ROCHE” is printed in blue ink on the light yellow body and "30 mg" is printed in blue ink on the light yellow cap.
TAMIFLU 45 mg capsules are available as grey hard gelatin capsules. “ROCHE” is printed in blue ink on the grey body and "45 mg" is printed in blue ink on the grey cap.
TAMIFLU 75 mg capsules are available as grey/light yellow hard gelatin capsules. “ROCHE” is printed in blue ink on the grey body and "75 mg" is printed in blue ink on the light yellow cap.
All three capsules strengths are available in blister packages of 10.
TAMIFLU Powder for Oral Suspension (6 mg/mL)
TAMIFLU powder for oral suspension contains 390 mg oseltamivir as oseltamivir phosphate per bottle, which when reconstituted contains 65 mL of suspension at a final concentration of 6 mg/mL oseltamivir.
A bottle of 13 g TAMIFLU powder for oral suspension contains 11.142 g of sorbitol. One dose of 45 mg oseltamivir administered twice daily delivers 2.6 g of sorbitol which is unsuitable for subjects with hereditary fructose intolerance (see 7 Warnings and Precautions, Endocrine and Metabolism).
TAMIFLU powder for oral suspension is available as a white powder blend for reconstitution to a white tutti-frutti-flavoured suspension. Available in 100 mL glass bottles with a bottle adapter and 1 oral dispenser*. Net contents after reconstitution: 65 mL containing oseltamivir phosphate equivalent to 390 mg oseltamivir base.
*Oral dosing dispenser manufactured by B. Braun Melsungen AG. 34209 Melsungen, Germany.
7. Warnings and Precautions
General
No increased efficacy was demonstrated in adult subjects receiving 150 mg TAMIFLU (oseltamivir phosphate) twice daily for 5 days compared to those receiving 75 mg twice daily for the treatment of influenza.
There is no evidence for efficacy of TAMIFLU in any illness caused by agents other than influenza viruses Types A and B. Data on treatment of influenza B are limited.
Efficacy of TAMIFLU in patients who begin treatment after 48 hours of symptoms has not been established.
Efficacy of TAMIFLU in the treatment of subjects with chronic cardiac disease and/or respiratory disease has not been established. No difference in the incidence of complications was observed between the treatment and placebo groups in this population. No information is available regarding treatment of influenza in patients with any medical condition sufficiently severe or unstable to be considered at imminent risk of requiring hospitalization.
Safety and efficacy of repeated treatment or prevention courses have not been studied.
Efficacy of TAMIFLU for treatment or prevention of influenza in immunocompromised patients has not been established.
Endocrine and Metabolism
A bottle of 13 g TAMIFLU powder for oral suspension contains 11.142 g of sorbitol. One dose of 45 mg oseltamivir administered twice daily delivers 2.6 g of sorbitol, which is unsuitable for subjects with hereditary fructose intolerance.
Hepatic/Biliary/Pancreatic
There have been post-marketing reports of elevated liver enzymes and hepatotoxicity including fulminant hepatitis/hepatic failure, in some cases with fatal outcome, where a causal relationship with oseltamivir could not be excluded, especially in patients with pre-existing liver disease.
The safety, efficacy and pharmacokinetics of oseltamivir in patients with severe hepatic impairment have not been studied (see 4 Dosage and Administration, 4.2 Recommended Dose and Dosage Adjustment, Dosage Adjustment, Hepatic Impairment).
Psychiatric
There have been post-marketing reports of delirium and self-injury, in some cases resulting in fatal outcomes, in patients with influenza who were receiving TAMIFLU. Because these events were reported voluntarily during clinical practice, estimate of frequency cannot be made but they appear to be uncommon based on TAMIFLU usage data. These events were reported primarily among pediatric patients. The contribution of TAMIFLU to these events has not been established. Patients with influenza should be closely monitored for signs of abnormal behaviour. If neuropsychiatric symptoms occur, the risks and benefits of continuing treatment should be evaluated for each patient (see 8 Adverse Reactions, 8.5 Post-Market Adverse Drug Reactions, Neurologic, and Psychiatric).
Influenza can be associated with a variety of neurologic and behavioural symptoms, which can include events such as hallucinations, delirium, and abnormal behaviour, in some cases resulting in fatal outcomes. These events may occur in the setting of encephalitis or encephalopathy, but can occur without obvious severe disease.
Renal
Renal Impairment: For dose adjustments in patients with renal impairment (for both treatment and prevention) - see 4 Dosage and Administration, 4.2 Recommended Dose and Dosage Adjustment, Dosage Adjustment, Renal Impairment.
The pharmacokinetics of oseltamivir have not been studied in patients with end-stage renal disease (i.e., creatinine clearance of < 10 mL/min) not undergoing dialysis. Hence, dosing recommendation cannot be provided for this group.
Sensitivity/Resistance
In clinical studies of naturally acquired infection, the cumulative incidence of oseltamivir-resistant virus by phenotyping alone or by phenotyping and genotyping was 0.32% (4/1245) or 0.4% (5/1245) respectively in adult/adolescent patients. In children with naturally acquired influenza virus infection, resistance was determined in 6 clinical studies WV15731 (0%; 0/5), WV15758 (8%; 15/183), WV15759/WV15871 (0%, 0/60), JV16284 (19%, 8/43), WV16193 (0%, 0/147), NV16871 (8%, 2/26). From the data obtained in these studies, the cumulative incidence of oseltamivir resistance in pediatric patients aged 1 to 12 years was 4.1% (19/464) based on phenotyping and 5.4% (25/464) based on phenotyping and genotyping (full genotyping was not performed on all patients). The patients cleared the virus normally and showed no clinical deterioration.
There has been no evidence for emergence of drug resistance associated with the use of TAMIFLU in clinical studies conducted to date in post-exposure (7 days), post-exposure within the household groups (10 days) and seasonal (42 days) prophylaxis of influenza in immunocompetent persons (see 15 Microbiology, Resistance).
Insufficient information is available to fully characterize the risk of emergence of resistance to TAMIFLU in clinical use (see 15 Microbiology, Resistance).
Skin
Severe skin and hypersensitivity reactions have been reported since marketing in patients treated with TAMIFLU (see 8 Adverse Reactions, 8.5 Post-Market Adverse Reactions).
7.1. Special Populations
7.1.1. Pregnancy
TAMIFLU should be used in pregnancy only if the potential benefits outweigh the potential risks to the fetus, taking into consideration the pathogenicity of the circulating influenza virus strain and the underlying condition of the pregnant woman.
A large amount of data from pregnant women exposed to oseltamivir (more than 1000 exposed outcomes during the first trimester) from post-marketing reports and observational studies indicate no direct or indirect harmful effects with respect to pregnancy. Results from a pooled pharmacokinetic analysis indicate a lower exposure to the active metabolite in pregnant women compared to non-pregnant women; however, this predicted exposure is expected to have clinical benefits and there are insufficient pharmacokinetic and safety data to recommend a dose adjustment in pregnant women who are justified to use TAMIFLU.
Studies for effects on embryo-fetal development were conducted in rats (50, 250 and 1500 mg/kg/day) and rabbits (50, 150 and 500 mg/kg/day) by the oral route. Relative exposures at these doses were, respectively, 2, 13 and 100 times human exposure in the rat and 4, 8 and 50 times human exposure in the rabbit. Pharmacokinetic studies indicated that fetal exposure was seen in both species. In the rat study, minimal maternal toxicity was reported in the 1500 mg/kg/day group. In the rabbit study, slight and marked maternal toxicities were observed, respectively, in the 150 and 500 mg/kg/day groups. An increased incidence of abortion was seen in the 500 mg/kg/day group. There was a dose-dependent increase in the incidence rates of a variety of minor skeletal individual abnormalities and variants in the exposed offspring in these studies. However, the individual incidence rate of each skeletal abnormality or variant remained within the background rates of occurrence in the species studied (see 16 Non-Clinical Toxicology).
7.1.2. Breastfeeding
Very limited information is available on children breast-fed by mothers taking oseltamivir and on excretion of oseltamivir in breast milk. In lactating rats, oseltamivir and the active metabolite are excreted in milk. Limited data demonstrated that oseltamivir and the active metabolite were detected in breast milk, however the levels were low, which would result in a sub-therapeutic dose to the infant. Based on this information, and the pathogenicity of the circulating influenza virus strain, administration of oseltamivir may be considered where the potential benefit to the lactating mother justifies the potential risk to the nursing infant.
7.1.3. Pediatrics
Pediatrics (< 1 year of age): TAMIFLU should not be used in children under 1 year of age (see 16 Non-Clinical Toxicology, General Toxicology, Multiple Dose Toxicity). The efficacy of TAMIFLU in infants younger than 1 year of age have not been established (see 14 Clinical Trials).
7.1.4. Geriatrics
Geriatrics (≥ 65 years of age): Efficacy of TAMIFLU in the treatment of elderly patients has not been evaluated. Safety data in 372 elderly patients (≥ 65 years old) showed no overall difference between these subjects and younger adults. Based on drug exposure and tolerability, dosage adjustments are not anticipated for elderly patients (see 10 Clinical Pharmacology, 10.3 Pharmacokinetics, Special Populations and Conditions, Geriatrics).
Safety has been demonstrated in elderly residents of nursing homes who took TAMIFLU for the prevention of influenza. Many of these individuals had cardiac and/or respiratory disease, and most had received vaccine that season (see 14 Clinical Trials).
- 8. Adverse Reactions
8.1. Adverse Reaction Overview
In adult/adolescent treatment studies with TAMIFLU (oseltamivir phosphate), the most frequently reported adverse events were nausea and vomiting. In the prevention studies, adverse events were qualitatively very similar to those seen in the treatment studies. In the pediatric treatment and prophylaxis studies, the most frequently reported adverse event was vomiting.
8.2. Clinical Trial Adverse Reactions
Clinical trials are conducted under very specific conditions. Therefore, the frequencies of adverse reactions observed in the clinical trials may not reflect frequencies observed in clinical practice and should not be compared to frequencies reported in clinical trials of another drug.
Adult Treatment Studies
In a total of 4624 patients, including patients on placebo and 75 mg b.i.d. TAMIFLU, in adult/adolescent Phase III studies in the treatment of influenza, the most frequently reported adverse events were nausea and vomiting. These events were transient and generally occurred with first dosing. These events did not lead to patient discontinuation of study drug in the vast majority of instances. At the recommended dose of 75 mg twice daily, the most frequently reported adverse events that led to patient withdrawal were nausea and vomiting.
In adult/adolescent Phase III treatment studies, some adverse events occurred more frequently in patients taking TAMIFLU compared to those taking placebo. The adverse events that occurred with an incidence of ≥ 1% at the recommended dose, either for treatment or prophylaxis, are shown in Table 5. This summary includes healthy young adults and “at risk” patients (patients at higher risk of developing complications associated with influenza e.g. elderly patients and patients with chronic cardiac or respiratory disease). Those events with an incidence of ≥ 1% and which were reported more frequently in patients taking TAMIFLU compared with placebo, irrespective of causality, were nausea, vomiting, abdominal pain and headache.
Table 5 - Most Frequent Adverse Events in Studies in Naturally Acquired Influenza for Adults/Adolescents for Treatment or Prophylaxis
Adverse Events System Organ Class (MedDRA) | Treatment* | Prevention | ||||||||||||||||
Adverse Events System Organ Class (MedDRA) | Treatment* | Prevention | ||||||||||||||||
TAMIFLU 75 mg twice daily for 5 days N=2647 | Placebo N=1977 | TAMIFLU 75 mg once daily N=1945 | Placebo N=1588 | |||||||||||||||
TAMIFLU 75 mg twice daily for 5 days N=2647 | Placebo N=1977 | TAMIFLU 75 mg once daily N=1945 | Placebo N=1588 | |||||||||||||||
| Ear and Labyrinth Disorders | ||||||||||||||||||
| Dizziness (incl. Vertigo)* | 54 | (2.0%) | 49 | (2.5%) | 28 | (1.4%) | 24 | (1.5%) | ||||||||||
| Gastrointestinal Disorders | ||||||||||||||||||
| Nausea (without vomiting) | 263 | (9.9%) | 118 | (6.0%) | 156 | (8.0%) | 66 | (4.2%) | ||||||||||
| Vomiting | 205 | (7.7%) | 63 | (3.2%) | 46 | (2.4%) | 19 | (1.2%) | ||||||||||
| Diarrhea* | 149 | (5.6%) | 147 | (7.4%) | 66 | (3.4%) | 66 | (4.2%) | ||||||||||
| Abdominal pain (incl. upper abdominal pain)* | 62 | (2.3%) | 51 | (2.6%) | 47 | (2.4%) | 31 | (2.0%) | ||||||||||
| Dyspepsia* | 12 | (0.5%) | 9 | (0.5%) | 29 | (1.5%) | 23 | (1.4%) | ||||||||||
| General Disorders and Administration Site Reactions | ||||||||||||||||||
| Fatigue* | 14 | (0.5%) | 9 | (0.5%) | 142 | (7.3%) | 107 | (6.7%) | ||||||||||
| Pain* | 8 | (0.3%) | 5 | (0.3%) | 70 | (3.6%) | 43 | (2.7%) | ||||||||||
| Pyrexia* | 6 | (0.2%) | 9 | (0.5%) | 33 | (1.7%) | 33 | (2.1%) | ||||||||||
| Pain in limb* | 5 | (0.2%) | 1 | (0.1%) | 20 | (1.0%) | 5 | (0.3%) | ||||||||||
| Influenza like illness* | ─ | ─ | 1 | (0.1%) | 21 | (1.1%) | 24 | (1.5%) | ||||||||||
| Infections and Infestations | ||||||||||||||||||
| Bronchitis | 70 | (2.6%) | 72 | (3.6%) | 10 | (0.5%) | 14 | (0.9%) | ||||||||||
| Sinusitis* | 35 | (1.3%) | 22 | (1.1%) | 15 | (0.8%) | 12 | (0.8%) | ||||||||||
| Herpes simplex* | 27 | (1.0%) | 23 | (1.2%) | 11 | (0.1%) | 9 | (0.6%) | ||||||||||
| Nasopharyngitis* | 4 | (0.2%) | 2 | (0.1%) | 80 | (4.1%) | 68 | (4.3%) | ||||||||||
| Upper respiratory tract infections* | 5 | (0.2%) | 1 | (0.1%) | 60 | (3.1%) | 51 | (3.2%) | ||||||||||
| Influenza* | ─ | ─ | ─ | ─ | 46 | (2.4%) | 41 | (2.6%) | ||||||||||
| Nervous System Disorders | ||||||||||||||||||
| Headache | 45 | (1.7%) | 27 | (1.4%) | 335 | (17.2%) | 260 | (16.4%) | ||||||||||
| Insomnia* | 31 | (1.2%) | 17 | (0.9%) | 22 | (1.1%) | 14 | (0.9%) | ||||||||||
| Respiratory, Thoracic and Mediastinal Disorders | ||||||||||||||||||
| Cough* | 42 | (1.6%) | 38 | (1.9%) | 94 | (4.8%) | 90 | (5.7%) | ||||||||||
| Nasal congestion* | 27 | (1.0%) | 22 | (1.1%) | 134 | (6.9%) | 113 | (7.1%) | ||||||||||
| Sore throat* | 25 | (0.9%) | 14 | (0.7%) | 100 | (5.1%) | 86 | (5.4%) | ||||||||||
| Rhinorrhea* | 6 | (0.02%) | 5 | (0.3%) | 29 | (1.5%) | 19 | (1.2%) | ||||||||||
| Musculoskeletal, Connective Tissue and Bone Disorders | ||||||||||||||||||
| Back pain* | 13 | (0.5%) | 9 | (0.5%) | 41 | (2.1%) | 41 | (2.6%) | ||||||||||
| Arthralgia* | 4 | (0.2%) | 3 | (0.2%) | 28 | (1.4%) | 39 | (2.5%) | ||||||||||
| Myalgia* | 7 | (0.3%) | 4 | (0.2%) | 20 | (1.0%) | 21 | (1.3%) | ||||||||||
| Disorders of Reproductive System and Breast | ||||||||||||||||||
| Dysmenorrhea* | ─ | ─ | ─ | ─ | 53 | (2.7%) | 51 | (3.2%) | ||||||||||
* These events may be related to the underlying influenza infection because they occurred either more frequently in patients on placebo compared to patients on TAMILFU, or the difference in frequency between the two arms was less than 1%.
Adult Prevention Studies
A total of 3533 subjects (adolescents, healthy adults and elderly) participated in 3 Phase III prevention studies, of whom 1480 received the recommended dose of 75 mg once daily. Adverse events were qualitatively similar to those seen in the treatment studies (see Table 5). There were no clinically relevant differences in the safety profile of the 942 subjects 65 years of age and older, who received TAMIFLU or placebo, compared with the younger population (aged up to 65 years).
In another study, an additional 399 subjects received 75 mg of TAMIFLU once daily for 10 days following the identification of a household index case. Similar to previous studies, nausea (8.3%), vomiting (4.5%), diarrhea (0.8%) and headache (7.8%) were among the most commonly reported adverse events.
8.2.1. Clinical Trial Adverse Reactions – Pediatrics
Pediatric Treatment Studies
A total of 1480 pediatric patients aged 1 to 12 years (including 698 otherwise healthy pediatric patients aged 1 to 12 and 334 asthmatic pediatric patients aged 6 to 12) participated in clinical studies of TAMIFLU given for the treatment of influenza. A total of 858 pediatric patients received treatment with TAMIFLU oral suspension.
Adverse events occurring in ≥ 1% of pediatric patients receiving TAMIFLU are listed in Table 6. The most frequently reported adverse event was vomiting. Other events reported more frequently by pediatric patients treated with TAMIFLU included abdominal pain, epistaxis, ear disorder and conjunctivitis. These events generally occurred once and resolved despite continued dosing. They did not cause discontinuation of drug in the vast majority of cases.
The adverse event profile in adolescents is similar to that described for adult patients and pediatric patients aged 1 to 12 years.
Table 6 - Most Frequent Adverse Events Occurring in Children Aged 1 to 12 Years in Studies in Naturally Acquired Influenza
Adverse Events System Organ Class (MedDRA) | Treatmenta | Prophylaxisb | ||||||||||||||
TAMIFLU 2 mg/kg twice daily N= 858 | Placebo N= 622 | Prophylaxis with TAMIFLUc N=148 | No Prophylaxisb N=87 | |||||||||||||
| Nervous System Disorders | ||||||||||||||||
| Headaches | 3 | (0.3%) | 5 | (0.8%) | 5 | (3.4%) | 1 | (1.1%) | ||||||||
| Blood and Lymphatic System Disorders | ||||||||||||||||
| Lymphadenopathy* | 5 | (0.6%) | 8 | (1.3%) | ─ | ─ | ||||||||||
| Ear and Labyrinth Disorders | ||||||||||||||||
| Earache* | 10 | (1.2%) | 4 | (0.6%) | 1 | (0.7%) | ─ | |||||||||
| Tympanic membrane disorder* | 4 | (0.5%) | 6 | (1.0%) | ─ | ─ | ||||||||||
| Eye Disorders | ||||||||||||||||
| Conjunctivitis (incl. red eyes, eye discharge and eye pain)* | 9 | (1.0%) | 2 | (0.3%) | ─ | ─ | ||||||||||
| Gastrointestinal Disorders | ||||||||||||||||
| Vomiting | 140 | (16.3%) | 51 | (8.2%) | 12 | (8.1%) | 2 | (2.3%) | ||||||||
| Diarrhea* | 63 | (7.3%) | 49 | (7.9%) | 1 | (0.7%) | ─ | |||||||||
| Abdominal pain (incl. upper abdominal pain)* | 29 | (3.4%) | 21 | (3.4%) | 3 | (2.0%) | ─ | |||||||||
| Nausea | 32 | (3.7%) | 27 | (4.3%) | 6 | (4.1%) | 1 | (1.1%) | ||||||||
Adverse Events
| System Organ Class (MedDRA) | Treatmenta | Prophylaxisb | |||||||||||||||
TAMIFLU 2 mg/kg twice daily N= 858 | Placebo N= 622 | Prophylaxis with TAMIFLUc N=148 | No Prophylaxisb N=87 | ||||||||||||||
| Dyspepsia* | 2 | (0.2%) | ─ | 3 | (2.0%) | ─ | |||||||||||
| Infections and Infestations | |||||||||||||||||
| Otitis media* | 43 | (5.0%) | 51 | (8.2%) | 3 | (2.0%) | 2 | (2.3%) | |||||||||
| Pneumonia* | 29 | (3.4%) | 19 | (3.1%) | ─ | 1 | (1.1%) | ||||||||||
| Bronchitis* | 14 | (1.6%) | 15 | (2.4%) | ─ | 2 | (2.3%) | ||||||||||
| Sinusitis* | 11 | (1.3%) | 13 | (2.1%) | 1 | (0.7%) | ─ | ||||||||||
| Nasopharyngitis* | 2 | (0.2%) | 2 | (0.3%) | 2 | (1.4%) | 4 | (4.6%) | |||||||||
| Upper respiratory tract infection* | 3 | (0.3%) | 3 | (0.5%) | 2 | (1.4%) | 3 | (3.4%) | |||||||||
| Respiratory, Thoracic and Mediastinal Disorders | |||||||||||||||||
| Cough* | 8 | (0.9%) | 4 | (0.6%) | 18 | (12.2%) | 23 | (26.4%) | |||||||||
| Nasal congestion* | 3 | (0.3%) | ─ | 16 | (10.8%) | 17 | (19.5%) | ||||||||||
| Asthma (including aggravated) | 22 | (2.6%) | 25 | (4.0%) | 2 | (1.4%) | 1 | (1.1%) | |||||||||
| Epistaxis* | 18 | (2.1%) | 14 | (2.3%) | 1 | (0.7%) | ─ | ||||||||||
| Rhinorrhoea* | 2 | (0.2%) | 2 | (0.3%) | 2 | (1.4%) | 1 | (1.1%) | |||||||||
| Skin and Subcutaneous Tissue Disorders | |||||||||||||||||
| Dermatitis* | 9 | (1.0%) | 11 | (1.8%) | ─ | ─ | |||||||||||
| General Disorders and Administration Site Reactions | |||||||||||||||||
| Pyrexia* | 2 | (0.2%) | 2 | (0.3%) | 3 | (2.0%) | 6 | (6.9%) | |||||||||
a Pooled data from Phase III trials of TAMIFLU treatment of naturally acquired influenza.
b Subjects participating in an uncontrolled household transmission study (in which household contacts received either TAMIFLU for prophylaxis (once-daily dosing for 10 days) or no prophylaxis but TAMIFLU treatment if they became ill), who remained on no prophylaxis and did not receive treatment with TAMIFLU.
c Pooled data from pediatric prophylaxis studies. Unit dose = age-based dosing (see 4 Dosage and Administration).
* These events may be related to the underlying influenza infection because they occurred either more frequently in patients on placebo compared to patients on TAMILFU, or the difference in frequency between the two arms was less than 1%.
Pediatric Prevention Studies
Amongst the 148 pediatric patients aged 1 to 12 years who received the recommended dose of TAMIFLU once daily, in a post-exposure prophylaxis study in households (N=99), and in a separate 6 week pediatric prophylaxis study (n=49), gastrointestinal events, particularly vomiting was the most frequently reported adverse event. Other events reported more frequently by pediatric patients who received TAMIFLU for prophylaxis are nausea, abdominal pain, dyspepsia and earaches. TAMIFLU was well tolerated in these studies and the adverse events noted were consistent with those previously observed in pediatric treatment studies (see Table 6).
Immunocompromised Patients: In a 12-week prophylaxis study in 475 immunocompromised subjects, including 18 children 1-12 years of age, the safety profile in the 238 subjects receiving TAMIFLU was consistent with that previously observed in TAMIFLU prophylaxis clinical trials.
8.3. Less Common Clinical Trial Adverse Reactions
Adult Treatment Studies
Additional adverse events occurring in < 1% of patients receiving TAMIFLU for treatment included unstable angina, anemia, pseudomembranous colitis, humerus fracture, pneumonia, pyrexia, and peritonsillar abscess.
8.4. Abnormal Laboratory Findings: Hematologic, Clinical Chemistry, and Other Quantitative Data
Not applicable.
8.5. Post-Market Adverse Reactions
The following adverse reactions have been identified during post-marketing use of TAMIFLU. Because these reactions are reported voluntarily from a population of uncertain size, it is not possible to reliably estimate their frequency or establish a causal relationship to TAMIFLU exposure.
Skin and hypersensitivity reactions: dermatitis, rash, eczema, urticaria, erythema multiforme, Stevens-Johnson-Syndrome, toxic epidermal necrolysis, anaphylactic/anaphylactoid reactions and face edema.
Hepatobiliary disorders: elevated liver enzymes, hepatotoxicity including fulminant hepatitis/hepatic failure, in some cases with fatal outcome.
Gastro-intestinal disorders: gastro-intestinal bleeding, hemorrhagic colitis.
Cardiac disorders: arrhythmia.
Neurologic: seizure.
Metabolism and nutrition disorders: aggravation of diabetes.
Psychiatric: delirium, including symptoms such as altered level of consciousness, confusion, abnormal behavior leading to self-injury, delusions, hallucinations, agitation, anxiety, nightmares (see 7 Warnings and Precautions).
9. Drug Interactions
9.2. Drug Interactions Overview
Oseltamivir is extensively converted to oseltamivir carboxylate by esterases, located predominantly in the liver. Drug interactions involving competition for esterases have not been extensively reported in literature. Low protein binding of oseltamivir and oseltamivir carboxylate suggests that the probability of drug displacement interactions is low.
In vitro studies demonstrated that neither oseltamivir nor the active metabolite are good substrates for P450 mixed-function oxidases or for glucuronyl transferases.
9.3. Drug-Behaviour Interactions
No drug-behavioural studies have been performed with TAMIFLU.
9.4. Drug-Drug Interactions
Cimetidine, a non-specific inhibitor of cytochrome P450 isoforms and competitor for renal tubular secretion of basic or cationic drugs, has no effect on plasma levels of oseltamivir or its active metabolite.
Clinically important drug interactions involving competition for renal tubular secretion are unlikely due to the known safety margin for most of these drugs, the elimination characteristics of the active metabolite (glomerular filtration and anionic tubular secretion) and the excretion capacity of these pathways. Co-administration of probenecid results in an approximate two-fold increase in exposure to the active metabolite due to a decrease in active anionic tubular secretion in the kidney. However, due to the wide safety margin of the active metabolite, no dose adjustments are required when co-administering with probenecid. Other drugs excreted via anionic tubular secretion have not been evaluated.
Co-administration with amoxicillin does not alter plasma levels of either compound, indicating that competition for the anionic secretion pathway is weak.
Co-administration with acetaminophen does not alter plasma levels of oseltamivir, its active metabolite, or paracetamol.
No pharmacokinetic interactions between oseltamivir or its major metabolite have been observed when co-administering oseltamivir with paracetamol, acetyl-salicylic acid, warfarin, rimantadine, amantadine, cimetidine or with antacids (magnesium and aluminum hydroxides and calcium carbonates).
In Phase III treatment and prophylaxis clinical studies, TAMIFLU (oseltamivir phosphate) has been administered with commonly used drugs such as ACE inhibitors (enalapril, captopril), thiazide diuretics (bendrofluazide), antibiotics (penicillin), H2-receptor blockers (cimetidine), and analgesic agents (acetylsalicylic acid, ibuprofen and paracetamol). No change in adverse event profile or frequency has been observed as a result of co-administration of TAMIFLU with these compounds.
9.5. Drug-Food Interactions
Interactions with food have not been established.
9.6. Drug-Herb Interactions
Interactions with herbal products have not been established.
9.7. Drug-Laboratory Test Interactions
Interactions with laboratory tests have not been established.
10. Clinical Pharmacology
Animal Pharmacology
Oseltamivir phosphate produced effects in the non-clinical safety pharmacology studies only at oral doses well in excess of any clinically relevant therapeutic levels. These effects in the rat, were reduced gastrointestinal transit and gastric emptying at 1000 mg/kg. In the rodent toxicology studies these effects were not reported as any sign of gastrointestinal disturbance. Additionally, there were increases in excretion of electrolytes at 100 and 1000 mg/kg and increased urine production at 1000 mg/kg. Increases in electrolyte excretion were reported in a 27-week rat toxicology study at 1000 mg/kg/day and attributed to a high phosphate intake due to the salt of the test material. In the same study less pronounced effects were seen at 200 mg/kg/day, while in another rat toxicology study no significant effects were seen at 100 mg/kg/day. A statistically significant increase in response to a painful stimulus was seen but this was neither time nor dose related and therefore not thought to be of pharmacological significance.
The intravenous infusion of the active metabolite at 2, 15 and 100 mg/kg cumulatively produced statistically significant changes in heart rate, QT and QTc interval, QRS duration and pCO2 when compared with time matched controls in the anaesthetized dog. The effects on heart rate and pCO2 were at isolated time points and the decrease in QRS duration was not accompanied by any other relevant physiological changes and so not likely to be due to the drug treatment. The statistical differences in QT and QTc interval between the active metabolite and vehicle treated groups was seen in the predose and just after the start of the infusion suggesting no pharmacological significance. Because of this, significance was tested for by comparing percentage changes from predose values within the active metabolite treatment group. There were no significant differences detected. However, on comparison with the absolute values significant differences were seen during the infusion of the 100 mg/kg/dose. To clarify this situation a further test was performed in an isolated sheep Purkinje fibre study where no significant effects were observed on cardiac action potential parameters. Other than these findings, no additional effects were seen on the cardiovascular and respiratory dynamics of the anaesthetized dog.
In conclusion, oseltamivir phosphate produced significant pharmacological effects only at doses much greater than would be of clinical relevance. It is therefore concluded that oseltamivir phosphate and the active metabolite produced no clinically relevant pharmacological effects on the central nervous, cardiovascular, respiratory, gastrointestinal, smooth muscle, renal, hepatic and immune systems tested.
Human Pharmacology
QT/QTc: A retrospective analysis of ECGs from 8 clinical pharmacology studies (n=182 subjects including 30 placebo) concluded that TAMIFLU (oseltamivir phosphate) does not cause prolongation of QT intervals in humans. Although some individuals were found to have some alterations in QTc measurements, none were of clinical significance and the frequency was similar among placebo and subjects treated with TAMIFLU.
In a study on ECG intervals in which healthy volunteers received daily doses of either 75, 225 or 450 mg TAMIFLU b.i.d. orally for 5 days, treatment with TAMIFLU had no impact on any ECG parameters.
10.1. Mechanism of Action
TAMIFLU (oseltamivir phosphate) is an ethyl ester prodrug requiring ester hydrolysis for conversion to the active metabolite, oseltamivir carboxylate. The active metabolite is a selective inhibitor of influenza
A and B virus neuraminidase enzymes which are glycoproteins found on the virion surface. Viral neuraminidase is primarily important for the release of recently formed virus particles from infected cells and the further spread of infectious virus in the body. The proposed mechanism of action of oseltamivir is via inhibition of influenza virus neuraminidase with the possibility of alteration of virus particle aggregation and release. It has also been suggested that neuraminidase can play a role in viral entry into uninfected cells.
Oseltamivir is readily absorbed after oral administration and converted by hepatic esterases to its active metabolite. The mean volume of distribution (Vss) of the active metabolite is approximately 23 L. The active metabolite is not further metabolized and is eliminated in the urine. The half-life of elimination of this metabolite is 6 to 10 hours. Renal clearance (18.8 L/h) exceeds glomerular filtration rate (7.5 L/h), indicating that tubular secretion in addition to glomerular filtration occurs. Also, the prodrug which reaches the systemic circulation (less than 5%) is eliminated by renal excretion. The binding of oseltamivir to human plasma protein is 42% and that of the active metabolite is negligible, approximately 3%.
Exposure to the active metabolite is inversely proportional to declining renal function.
10.2. Pharmacodynamics
Refer to Section 10.1 Mechanism of Action. Additional information in the Product Monograph not included at the time of authorization.
10.3. Pharmacokinetics
Absorption
Oseltamivir is readily absorbed from the gastrointestinal tract after oral administration of TAMIFLU and is extensively converted predominantly by hepatic esterases to the active metabolite. At least 75% of an oral dose reaches the systemic circulation as the active metabolite. Exposure to the prodrug is less than 5% relative to the active metabolite. Plasma concentrations of active metabolite are proportional to dose and are not significantly affected by co-administration with food (see 4 Dosage and Administration).
Distribution
The mean volume of distribution (Vss) of the active metabolite is approximately 23 litres in humans.
The binding of oseltamivir to human plasma protein is 42% and that of the active metabolite is negligible, approximately 3%.
Metabolism
Oseltamivir is extensively converted to the active metabolite by esterases located predominantly in the liver. Neither oseltamivir nor the active metabolite are substrates for, or inhibitors of, cytochrome P450 isoforms.
Elimination
Absorbed oseltamivir is primarily (> 90%) eliminated by conversion to the active metabolite. The active metabolite is not further metabolized and is eliminated in the urine. Peak plasma concentrations of the active metabolite decline with a half-life of 6 to 10 hours in most subjects. The active drug is eliminated entirely (> 99%) by renal excretion. Renal clearance (18.8 L/h) exceeds glomerular filtration rate (7.5 L/h), indicating that tubular secretion in addition to glomerular filtration occurs. Less than 20% of an oral radiolabelled dose is eliminated in feces.
Special Populations and Conditions
Pediatrics: The pharmacokinetics of oseltamivir have been evaluated in single dose pharmacokinetic studies in pediatric patients aged 1 to 16 years. Multiple dose pharmacokinetics were studied in a small number of pediatric patients aged 3-12 years enrolled in a clinical trial. Younger pediatric patients cleared both the prodrug and the active metabolite faster than adults resulting in lower exposure for a given mg/kg dose. Doses of 2 mg/kg give oseltamivir carboxylate exposures comparable to those achieved in adults receiving a single 75 mg capsule dose (approximately 1 mg/kg). The pharmacokinetics of oseltamivir in pediatric patients over 12 years of age is similar to those in adults.
TAMIFLU should not be used in children under 1 year of age (see 16 Non-Clinical Toxicology, General Toxicology, Multiple Dose Toxicity).
- Geriatrics: Exposure to the active metabolite at steady-state was 25% to 35% higher in elderly patients (age range 65 to 78) compared to young adults given comparable doses of TAMIFLU. Half-lives observed in the elderly patients were similar to those seen in young adults. On the basis of drug exposure and tolerability, dosage adjustments are not required for elderly patients for either treatment or prevention (see 4 Dosage and Administration, 4.2 Recommended Dose and Dosage Adjustment, Dosage Adjustment).
- Hepatic Insufficiency: The safety, efficacy and pharmacokinetics of TAMIFLU in patients with severe hepatic impairment have not been studied (see 7 Warnings and Precautions, Hepatic/Biliary/Pancreatic). In a clinical study of adult patients with moderate hepatic impairment (N=11), compared with healthy volunteers (N=23), metabolic conversion of oseltamivir into the active metabolite oseltamivir carboxylate was not significantly altered (see 4 Dosage and Administration, 4.2 Recommended Dose and Dosage Adjustment, Dosage Adjustment, Hepatic Impairment). No studies have been carried out in pediatric patients with hepatic impairment.
- Renal Insufficiency: Administration of 100 mg of TAMIFLU twice daily for five days to patients with various degrees of renal impairment showed that exposure to the active metabolite is inversely proportional to declining renal function. For dosage information, see 4 Dosage and Administration, Dosage Adjustment.
- Storage, Stability, and Disposal
TAMIFLU (oseltamivir phosphate) Capsules: Store at 15-25°C.
TAMIFLU Powder for Oral Suspension: Store dry powder at 15-25°C.
Store reconstituted suspension:
- a)
At room temperature (not above 25°C). Discard unused portion within 10 days of reconstitution.
or
- b) In a refrigerator (2-8°C). Discard unused portion within 17 days of reconstitution.
Do not freeze reconstituted suspension.
TAMIFLU Pharmacy-Compounded Suspension:
Store reconstituted suspension:
Compounded with Ora-Sweet®SF, simple syrup or cherry syrup:
- Room temperature storage conditions: Stable for five days (5 days) when stored at 25°C.
- Refrigerated storage conditions: Stable for 5 weeks (35 days) when stored in a refrigerator at 2-8°C.
Compounded with purified water containing 0.05% w/v sodium benzoate added as preservative:
- Room temperature storage conditions: Stable for 10 days when stored at room temperature. Do not store above 25°C.
- Refrigerated storage conditions: Stable for 49 days when stored at 2-8°C.
Note: The storage conditions are based on stability studies of compounded oral suspensions, using the above mentioned vehicle, which were placed in amber glass and amber polyethyleneterephthalate (PET) bottles. Stability studies have not been conducted with other vehicles or bottle types.
TAMIFLU should not be used after the expiry date (EXP) shown on the pack.
Disposal of unused/expired medicines
The release of pharmaceuticals in the environment should be minimized. Medicines should not be disposed of via wastewater and disposal through household waste should be avoided.
Any unused medicinal product or waste materials should be disposed of in accordance with local requirements.
Part 2: Scientific Information
13. Pharmaceutical Information
Drug Substance
Non-proprietary name of the drug substance(s):
oseltamivir phosphate
Chemical name:
Ethyl (3R, 4R, 5S)-4-acetamido-5-amino-3-(1-ethylpropoxy)-1-cyclohexene-1-carboxylate, phosphate (1:1)
Molecular formula and molecular mass:
C16H28N2O4 (free base)
312.4 for oseltamivir free base and 410.4 for oseltamivir phosphate salt
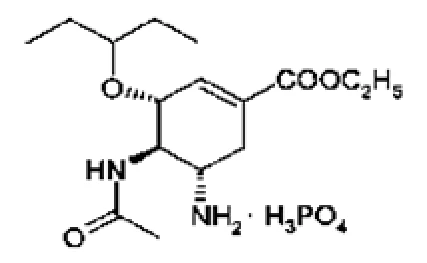
Structural formula:
Physicochemical properties:
- Physical Form: White crystalline solid
- Solubility: Freely soluble in water and methanol, slightly soluble in dimethylformamide and ethanol, and practically insoluble in acetone, 2-propanol and non-polar organic solvents.
- pKa and pH values: pKa: 7.75
- Partition Co-efficient: 1-octanol/aqueous phosphate buffer: logP=0.36
- Melting Point: 192-195°C with degradation
14. Clinical Trials
14.1. Clinical Trials by Indication
Treatment of Influenza
Adult Patients: Phase III clinical trials evaluated the safety and efficacy of TAMIFLU (oseltamivir phosphate) for the treatment of naturally occurring influenza during a period when influenza virus was known to be circulating in the community. A total of 1418 patients received any treatment (TAMIFLU or placebo) of whom 476 patients received 75 mg TAMIFLU twice daily for 5 days. Patients started treatment with TAMIFLU within 40 hours after reported onset of symptoms. The primary efficacy parameter was the time to alleviation of all symptoms. The population used in the primary analyses was the intent-to-treat-infected (ITTI) population. This population included only subjects who received at least one dose of study treatment and who had laboratory confirmed influenza. An intent-to-treat (ITT) population included all subjects who took at least one dose of study medication, regardless of whether they proved to have influenza.
The results for two pivotal studies (WV15670 and WV15671) are shown in Table 7.
Table 7 - Median Time (Hours) to Alleviation of All Symptoms in the ITTI and ITT Populations
| Study | Population | Placebo (95% CI) | TAMIFLU 75 mg twice daily (95% CI) | p-value* |
| WV15670 | ITTI | n=161 116.5 (101.5 to 137.8) | n=157 87.4 (73.3 to 104.7) | 0.017 |
| ITT | n=235 116.1 (99.8 to 129.5) | n=240 97.6 (79.1 to 115.3) | 0.051 | |
| WV15671 | ITTI | n=128 103.3 (92.6 to 118.7) | n=121 71.5 (60.0 to 83.2) | < 0.0001 |
| ITT | n=200 97.0 (86.3 to 113.6) | n=204 76.3 (66.3 to 89.2) | 0.004 |
ITT intent-to-treat
ITTI intent-to-treat infected
* difference between medians
Treatment with TAMIFLU significantly reduced the duration by 1.3 days, of clinically relevant symptoms of influenza. The seven symptoms assessed were: feverish feeling, muscle aches or myalgia, headache, sore throat, cough, overall discomfort, and nasal stuffiness or runny nose.
Pediatric Patients: One double-blind placebo controlled treatment trial was conducted in pediatric patients, aged 1 to 12 years (mean age 5.3), who had fever (> 100°F) plus one respiratory symptom (cough or coryza) when influenza virus was known to be circulating in the community. In this study, 67% of influenza-infected patients were infected with influenza A and 33% with influenza B.
Treatment with TAMIFLU, started within 48 hours of onset of symptoms, significantly reduced the duration of illness by 1.5 days compared to placebo. Duration of illness was defined as time to alleviation of cough, alleviation of coryza, resolution of fever, and return to normal health and activity.
Prevention of Influenza
Adult Patients: The efficacy of TAMIFLU in preventing naturally occurring influenza illness has been proven in four separate trials which are summarized below and in Table 8.
In a Phase III study (WV15799) in adult and adolescent contacts of a household case of influenza, administered 75 mg of TAMIFLU once daily, starting within 2 days of onset of symptoms in the household case and continued for 7 days, significantly reduced the incidence of influenza illness occurring in the contacts by 92% (p value = < 0.001).
In a double blind placebo controlled study (WV15673) conducted in unvaccinated otherwise healthy adults 18-65 years of age, 75 mg of TAMIFLU administered once daily significantly reduced the incidence of clinical influenza by 76% (p value = 0.0006) during a community outbreak of influenza. The subjects in this study received TAMIFLU for a period of 42 days. No additional benefit was demonstrated in this study using 75 mg of TAMIFLU twice daily.
In a double blind placebo controlled study (WV15825) in elderly residents of nursing homes, many of whom had chronic cardiac disease and/or respiratory disease, 80% received vaccine in the season of the study. The vaccine was a good match for circulating strains. The administration of 75 mg of TAMIFLU once daily significantly reduced the incidence of clinical influenza illness in these patients by 92% (p value = 0.0015). In the same study, TAMIFLU significantly reduced the incidence of influenza associated bronchitis, pneumonia and sinusitis by 86% (p value = 0.037). The subjects in this study received TAMIFLU for a period of 42 days.
In all three of these clinical trials (WV15799, WV15673 and WV15825), approximately 1% of subjects taking TAMIFLU for prevention developed influenza during the dosing period.
In a fourth Phase III study (WV16193), it was demonstrated that TAMIFLU effectively prevents the secondary spread of influenza within households. In this study, the index case was treated with TAMIFLU and household contacts were randomized (by household) to receive either prophylaxis (P) with TAMIFLU or treatment (T) with TAMIFLU upon emergence of influenza-like illness. In households with infected index cases where subjects who were already shedding virus at baseline were excluded (ITTIINAB population) there was a 78.8% (p =0.0008) reduction in the incidence of laboratory-confirmed influenza in P versus T. Amongst contacts, the outcome was analogous to that seen for households with a significantly lower number of infected contacts in P versus T (84.5% reduction, p =0.0002, ITTIINAB population). No virus shedding was detected in any subject in the prophylaxis group while 7% of contact in the treatment group (ITTIINAB) shed virus.
TAMIFLU also significantly reduced the incidence of virus shedding and successfully prevented virus transmission in families.
Table 8 - Clinical Summary of Prevention Studies
| Study | Number of Subjects | Dose | Reduction in Clinical Influenza (Protective Efficacy) |
| Seasonal Studies | |||
| ITT Population | |||
WV15673/WV15697 Adults | 1559 | Placebo 75 mg o.d. 75 mg b.i.d. 42 days | 76%, p = 0.00055 72%, p = 0.00125 |
WV15825 Elderly | 548 | Placebo 75 mg o.d. 42 days | 92%, p = 0.00153 |
| Post-exposure Studies | |||
| ITTIINAB Population | |||
WV15799 Adult/adolescent contacts, index case not treated | 405 | Placebo 75 mg o.d., 7 days | 92%, p =0.000076 |
WV16193 Index case treated, age ≥ 1 year | 89** | Prophylaxis: 75 mg o.d., 10 days* Treatment: 75 mg b.i.d., 5 days* | 78.8%, p = 0.0008 |
| WV16193 (children 1-12 years) | 117 | Prophylaxis: 30 mg (1-2 years) 45 mg (3-5 years) 60 mg (6-12 years) o. d., 10 days Treatment: 30 mg (1-2 years) 45 mg (3-5 years) 60 mg (6-12 years) b. i. d., 5 days | 80.1% (22.0-94.9), p = 0.0206 |
*Pediatric dosing adjusted according to age
** Number of households
ITT=Intent to treat
ITTIINAB=Intent to treat, index infected, not infected at baseline
Pediatric Patients
In the post-exposure prophylaxis study in the family (WV16193; see ‘Adult Prevention Studies’) there were 215 pediatric contact cases (> 1 to 12 years of age). There was an even distribution of boys and girls with the majority being Caucasian. The mean age was 8 years (range 1 to 12). The data from this subset of pediatric patients was examined to determine if oseltamivir was effective in the prevention of influenza infection in this setting. When subjects who were already shedding virus at baseline were excluded (ITTIINAB population, 117), 17 pediatric contacts became infected, 2 in the prophylaxis group and 15 in the treatment group (see Table 8). The protective efficacy in the pediatric contacts was similar to that achieved in the overall population in this study.
The dosing schedule in this study was by age. The majority of children received the now recommended schedule of treatment by weight in children (see 4 Dosage and Administration). There were, however, some children who were under- or over-dosed (23% and 9%, respectively) in this study.
Prophylaxis of Influenza in Immunocompromised Patients
A double-blind, placebo-controlled study was conducted for seasonal prophylaxis of influenza in 475 immunocompromised subjects (including 18 pediatric subjects 1 to 12 years of age) who had received solid organ (n=388; liver, kidney, liver and kidney) or hematopoietic stem cell transplants (n=87). Median time since transplant for solid organ transplant recipients was 1105 days for the placebo group and 1379 days for the oseltamivir group. Median time since transplant for hematopoietic stem cell transplant recipients was 424 days for the placebo group and 367 days for the oseltamivir group. Approximately 40% of subjects received influenza vaccine prior to entering the study. The primary efficacy endpoint for this study was the incidence of confirmed, clinical influenza, defined as oral temperature > 99.0°F/37.2°C plus cough and/or coryza, all recorded within 24 hours, plus either a positive virus culture or a four-fold increase in virus antibody titers from baseline. The incidence of confirmed clinical influenza was 3% (7/238) in the group not receiving TAMIFLU compared with 2%
(5/237) in the group receiving TAMIFLU; this difference was not statistically significant. A secondary analysis was performed using the same clinical symptoms and RT-PCR for laboratory confirmation of influenza. Among subjects who were not already shedding virus at baseline, the incidence of RT-PCR confirmed clinical influenza was 3% (7/231) in the group not receiving TAMIFLU and < 1% (1/232) in the group receiving TAMIFLU.
15. Microbiology
Virology: Oseltamivir was also tested for its effect on human T cell proliferation in vitro. Both antigen specific T cell lines and peripheral blood lymphocytes were isolated from whole blood. There was a slight but significant inhibition of influenza specific T cell line proliferation in the presence of 1 and 10 µM active metabolite, while there was no effect on antigen stimulation of peripheral blood lymphocytes. This slight effect (< 20%) on T cell proliferation is unlikely to compromise the long-term immune status of the patient with respect to subsequent influenza infection.
The active metabolite inhibits neuraminidases of influenza viruses of both types A and B. Inhibitory concentrations in vitro are in the low nanomolar range. The 50% inhibitory concentration (IC50) was in the range of 0.1 to 2.6 nM. The relationship between the in vitro antiviral activity in cell culture and the inhibition of influenza virus replication in humans has not been established. The active metabolite also inhibits influenza virus infection and replication in vitro and inhibits influenza virus replication and pathogenicity in animal models.
Resistance:
In vitro
Extensive in vitro work has been completed with the active metabolite. Resistance to this compound does not arise readily in vitro. Several different resistance mutations in the viral neuraminidase have been selected in vitro in Roche studies or reported in the published literature. Resistance mutations tend to be viral sub-type specific. The degree of reduced sensitivity differs markedly for different mutations from 2 fold for I222V in N1 to 30,000 fold for R292K in N2. Influenza A virus H1N1 strains are associated with a histidine to tyrosine change at position 274 (H274Y) on the enzyme. In H3N2 subtypes the genetic alteration of interest is an arginine to lysine at position 292 (R292K) on the enzyme. In vitro these mutant viruses exhibit reduced growth potential compared to wild-type virus.
In vivo
In vivo experiments of infectivity and pathogenicity have been conducted with mutated viruses in mice and ferrets. These experiments have demonstrated that the H274Y H1N1 mutant and the R292K H3N2 mutant have reduced ability to infect susceptible animals compared to wild-type virus and that infection is not associated with clinical evidence of pathogenicity in the ferret. Correlation of in vitro resistance patterns to resistance in vivo is not known. Viruses with resistant neuraminidase genotypes have varying degrees of loss of fitness compared to wild-type.
Treatment of Influenza
Clinical Studies
The risk of emergence of influenza viruses with reduced susceptibility or resistance to oseltamivir has been examined during Roche-sponsored clinical studies. Patients who were found to carry oseltamivir-resistant virus generally did so transiently, and showed no worsening of the underlying symptoms. In some pediatric patients, oseltamivir-resistant virus was detected for a prolonged period compared to patients carrying oseltamivir-sensitive virus; however these patients showed no prolongation of influenza symptoms.
In immunocompromised adults and pediatrics (1 year of age and older), selection of influenza viruses resistant oseltamivir can occur at higher frequencies than in the otherwise healthy population. In a treatment study of immunocompromised subjects, treatment‐associated genotypic resistance was detected in 27% (8/30), 12% (6/52), and 0% (0/42) of influenza A/H1N1, A/H3N2, and B virus infections, respectively. Treatment‐emergent resistance was observed at a higher frequency in hematopoietic stem cell transplant recipients (32%; 6/19).
Table 9 - Incidence of Oseltamivir Resistance in Clinical Studies
| Patient Population | Patients with Resistance Mutations (%) |
| Phenotyping | Geno- and Phenotyping* |
| Adults and adolescents | |
| 4/1245 (0.32%) | 5/1245 (0.4%) |
| Children (1-12 years) | |
| 19/464 (4.1%) | 25/464 (5.4%) |
* Full genotyping was not performed in all studies.
Insufficient information is available to fully characterize the risk of emergence of resistance to TAMIFLU in clinical use.
Prevention of Influenza
There has been no evidence for emergence of drug resistance associated with the use of TAMIFLU in clinical studies conducted to date in post-exposure (7 days), post-exposure within household contacts (10 days) and seasonal (42 days) prevention of influenza in immunocompetent subjects.
Clinical and surveillance data: Natural mutations associated with reduced susceptibility to oseltamivir in vitro have been detected in influenza A and B viruses isolated from patients without exposure to oseltamivir. For example, in 2008 the oseltamivir resistance-associated substitution H275Y was found in > 99% of circulating 2008 H1N1 influenza isolates in Europe, while the 2009 H1N1 influenza (“swine flu”) was almost uniformly susceptible to oseltamivir. Resistant strains have also been isolated from both immunocompetent and immunocompromised patients treated with oseltamivir. The susceptibility to oseltamivir and the prevalence of such viruses appears to vary seasonally and geographically. Oseltamivir resistance has also been reported in patients with pandemic H1N1 influenza in connection with both therapeutic and prophylactic regimens.
The rate of emergence of resistance may be higher in the youngest age groups, and in immunocompromised patients. Oseltamivir-resistant viruses isolated from oseltamivir-treated patients and oseltamivir-resistant laboratory strains of influenza viruses have been found to contain mutations in N1 and N2 neuraminidases. Resistance mutations tend to be viral sub-type specific.
Prescribers should consider available information on influenza virus drug susceptibility patterns for each season when deciding whether to use TAMIFLU (for latest information, please refer to WHO and/or local government websites).
Cross resistance:
Cross-resistance between zanamivir-resistant influenza mutants and oseltamivir-resistant influenza mutants has been observed in vitro.
Due to the limitations in the assays available to detect drug-induced shifts in virus susceptibility due to mutations in the viral hemagglutinin, an estimate of the incidence of oseltamivir resistance and possible cross-resistance to zanamivir in clinical isolates cannot be made. However, one of the three oseltamivir-induced mutations in the viral neuraminidase from clinical isolates is the same as one of the three mutations in the viral neuraminidase from clinical isolates observed in zanamivir-resistant virus.
Insufficient information is available to fully characterize the risk of emergence of resistance or cross-resistance to TAMIFLU (oseltamivir phosphate) in clinical use.
16. Non-Clinical Toxicology
General toxicology
Acute Dose Toxicity
Acute oral administration was well tolerated by male and female adult rodents (mice and rats) and unweaned 14-day old male and female rats at 2000 mg/kg (~1000-fold the highest clinical dose). Single oral administration of 500 mg/kg (free base, corresponding to 657 mg/kg phosphate salt dose) or higher to juvenile 7-day old rats resulted in treatment-related mortality together with functional observation battery findings (FOB) and clinical signs indicative of general toxicity and imminent mortality (including low arousal, tremors, convulsions, alterations in general body posture, respiration, mucous membrane and skin colouration, and/or hypoactivity) and reduced body weight gain. The no effect level was 300 mg/kg (free base, corresponding to 394 mg/kg phosphate salt dose; ~150-fold the highest clinical dose) in juvenile rats in that study.
An intravenous range-finding study in mice (n=1/sex/dose) produced convulsions immediately after intravenous dosing with 250 mg/kg. The male died and the female recovered after 40 minutes. The maximum non-lethal dose of 100 mg/kg was confirmed in a further five males and five females observed for two weeks. Other than some evidence of a local reaction in the tail of two females, there were no significant adverse effects in this group.
Multiple Dose Toxicity
In multiple dose rat studies, doses up to 500 mg/kg/day (2 weeks), 650 mg/kg/day (4 weeks), and 200 mg/kg/day (27 weeks) were generally well tolerated, with no significant toxicologic effects.
A dose of 1000 mg/kg/day in a two week range finding rat study in unweaned 7-9 day old rats resulted in a high rate of mortality (18/24). At 500 mg/kg, no adverse effects were seen in the 7-9 day old rats or repeated treatment (500 mg/kg/day administered from 7 to 21 days post-partum).
In multiple dose rat studies, the highest doses examined (≥ 1000 mg/kg/day) also induced two renal changes. One consisted of cortico-medullary mineralisation in the proximal tubules due to the imbalance of the calcium/phosphate ratio in the diet caused by dosing high levels of a phosphate salt. The second was a mild enhancement of chronic progressive nephropathy; rats are specifically sensitive to both these changes. A dose of 1000 mg/kg/day in the rat results in approximately 70 and 520 times the clinical exposure in humans, to the active metabolite and prodrug, respectively. In clinical studies, there was no biochemical evidence of renal effects in humans.
Marked gastrointestinal irritation was observed in marmosets at 2000 mg/kg/day, but not in four- and 39-week studies at 2 x 500 mg/kg/day. Emesis occurred at 500 mg/kg/day and above in marmosets, probably related to the concentration of the oral formulation. A reduction in incidence was associated with dividing the doses and halving the concentrations administered. This effect was seen at approximately 100 and 200 times the exposure values following clinical use in human, of the active metabolite and prodrug, respectively.
In the 39-week marmoset study, one 2 x 25 mg/kg/day group and two 2 x 100 mg/kg/day group animals were sacrificed prematurely. All three showed evidence of osteomalacia before dosing commenced, at autopsy and at the histopathological examination of the bones. No animal in the 2 x 500 mg/kg/day group was affected. Review of the clinical safety database, including the elderly, failed to reveal any biochemical evidence of skeletal effects in humans.
Genotoxicity
There was no evidence of mutagenic potential in any study (doses up to 5000 µg/plate), with or without metabolic activation. Separate bacterial cell gene mutation (Ames) tests were conducted for the pro drug and active metabolite. A mouse lymphoma cell mutation test examined the active metabolite. The pro drug was tested in a chromosome analysis assay with human lymphocytes, and in an in vivo micronucleus test in mice (oral dose of up to 2000 mg/kg). All the study systems were verified as sensitive by positive controls, and all the results were negative.
Two year rat and mouse studies and a six month transgenic Tg: AC mouse assay performed with the active metabolite were negative.
Reproductive and developmental toxicology
Fertility, teratology and pre- and post-natal studies were conducted to cover all phases of the reproductive process. There was no evidence of adverse effects on fertility or embryo-foetal development up to the highest dose of 1500 mg/kg/day in rats, or for teratogenicity testing in rabbits up to 500 mg/kg/day. These dose levels were associated with maternal toxicity. In rabbits mortalities occurred at 750 and 1500 mg/kg/day during a non-pregnant tolerance study. Some rabbits were sacrificed in the teratology range-finding and main studies at 500 mg/kg/day due to abortions associated with maternal toxicity. In the regulatory pre- and post-natal study in rats, maternal deaths occurred (9/25) at or immediately prior to delivery in the 1500 mg/kg/day group; prolonged parturition was also observed. Two further studies were therefore undertaken; although only 1/125 maternal deaths at parturition were seen in the combined 1500 mg/kg/day groups, extension of parturition was confirmed by these studies. It was concluded that the drug alone was not responsible for the maternal deaths in the first pre- and post-natal study.
At 1500 mg/kg/day in the rat teratology study, there was a slightly increased incidence of incomplete ossification of the 3rd sternebra in the exposed offspring, when compared to controls. Statistical significance was achieved, however, the majority of incidences occurred in one litter, where a general reduction in ossification was observed. In view of the isolated nature of this finding it was considered to be of doubtful toxicological significance.