


Product Monograph - Taro-Lurasidone
SUMMARY PRODUCT INFORMATION
| Route of Administration | Dosage Form / Strength | Nonmedicinal Ingredients |
| Oral | Film-Coated Tablets / 20 mg, 40 mg, 60 mg, 80 mg, and 120 mg | Mannitol, pregelatinized starch, alginic acid, croscarmellose sodium, colloidal silicon dioxide, magnesium stearate, Opadry® (hypromellose, titanium dioxide, macrogol, carnauba wax); 80 mg tablet also contains: iron oxide yellow, FD&C blue #1, and ferrosoferic oxide. |
INDICATIONS AND CLINICAL USE
Adults
Schizophrenia
Taro-Lurasidone (lurasidone hydrochloride tablets) is indicated for the management of the manifestations of schizophrenia.
The antipsychotic efficacy of lurasidone hydrochloride tablets was established in short-term (6-week) controlled trials [see CLINICAL TRIALS]. The efficacy of lurasidone hydrochloride tablets in long-term use, that is, for more than 6 weeks, has not been systematically evaluated in controlled trials of patients with manifestations of schizophrenia.
Depressive Episodes Associated with Bipolar I Disorder
Taro-Lurasidone is indicated as monotherapy or as adjunctive therapy with lithium or valproate for the acute management of depressive episodes associated with bipolar I disorder.
The efficacy of lurasidone hydrochloride tablets for long-term use, that is, for more than 6 weeks, has not been systematically evaluated in controlled studies. The physician who elects to use Taro-Lurasidone for extended periods should periodically re-evaluate the long term usefulness of the drug for the individual patient.
Geriatrics (>65 years of age):
Taro-Lurasidone is not indicated in elderly patients with dementia [see WARNINGS AND PRECAUTIONS, Serious Warnings and Precautions Box and Special Populations]. The safety and efficacy of lurasidone hydrochloride tablets in patients 65 years of age or older have not been established.
Pediatrics (<18 years of age)
When prescribing to adolescents with schizophrenia or adolescents with depressive episodes associated with bipolar I disorder, clinicians must take into account the safety concerns associated with all antipsychotic drugs which include: extrapyramidal effects, hyperglycemia, weight gain, and hyperlipidemia, which can be more frequent or more severe in this patient population than in adults [see WARNINGS AND PRECAUTIONS and ADVERSE REACTIONS]. Taro-Lurasidone should only be prescribed to adolescents with schizophrenia or bipolar I disorder by clinicians who are experienced in the diagnosis and treatment of adolescents with psychiatric illness and who are experienced in the early detection and management of the above-mentioned safety issues associated with this class of drugs.
Schizophrenia
Taro-Lurasidone is indicated for the management of the manifestations of schizophrenia in adolescents (15-17 years).
The safety and efficacy of lurasidone hydrochloride tablets were evaluated in one short-term (6 week) controlled trial in adolescents (13-17 years) [see CLINICAL TRIALS]. Taro-Lurasidone is not indicated for the treatment of schizophrenia in adolescents less than 15 years of age due to insufficient safety and efficacy data [see ADVERSE REACTIONS, CLINICAL TRIALS, Schizophrenia, Adolescents].
The efficacy of lurasidone hydrochloride tablets in long-term use, that is, for more than 6 weeks, has not been systematically evaluated in controlled trials of patients with manifestations of schizophrenia. The physician who elects to use Taro-Lurasidone for extended periods in adolescents with manifestations of schizophrenia should periodically re-evaluate the long term usefulness of the drug for the individual patient. The safety and efficacy of lurasidone hydrochloride tablets in schizophrenia patients less than 13 years of age have not been evaluated.
Depressive Episodes Associated with Bipolar I Disorder
Taro-Lurasidone is indicated as monotherapy for the acute management of depressive episodes associated with bipolar I disorder in adolescent (13 to 17 years) patients.
The safety and efficacy of lurasidone hydrochloride tablets 20 to 80 mg/day for the treatment of bipolar depression in children and adolescents (10 to 17 years) was evaluated in a 6-week, placebo-controlled clinical study in 343 children and adolescents. Taro-Lurasidone is not indicated for the treatment of depressive episodes in bipolar I disorder in patients less than 13 years of age due to insufficient safety and efficacy data [see ADVERSE REACTIONS, DOSAGE AND ADMINISTRATION and CLINICAL TRIALS].
CONTRAINDICATIONS
Taro-Lurasidone (lurasidone hydrochloride) is contraindicated in any patient with a known hypersensitivity to lurasidone hydrochloride or any components in the formulation [for a complete listing, see DOSAGE FORMS, COMPOSITION AND PACKAGING]. Angioedema has been observed with lurasidone [see ADVERSE REACTIONS].
Taro-Lurasidone is contraindicated with strong CYP3A4 inhibitors (e.g., ketoconazole) and strong CYP3A4 inducers (e.g., rifampin) [see DRUG INTERACTIONS].
WARNINGS AND PRECAUTIONS
General
Body Temperature Regulation
Disruption of the body’s ability to reduce core body temperature has been attributed to antipsychotic agents. Appropriate care is advised when prescribing Taro-Lurasidone (lurasidone hydrochloride) for patients who will be experiencing conditions that may contribute to an elevation in core body temperature, e.g., exercising strenuously, exposure to extreme heat, receiving concomitant medication with anticholinergic activity, or being subject to dehydration.
Carcinogenesis and Mutagenesis
For animal data, see TOXICOLOGY.
Cardiovascular
Orthostatic Hypotension and Syncope
Taro-Lurasidone may cause orthostatic hypotension, perhaps due to its α1-adrenergic receptor antagonism.
Serious Warnings and Precautions
Increased Mortality in Elderly Patients with Dementia.
Elderly patients with dementia treated with atypical antipsychotic drugs are at an increased risk of death compared to placebo. Analyses of thirteen placebo-controlled trials with various atypical antipsychotics (modal duration of 10 weeks) in these patients showed a mean 1.6-fold increase in the death rate in the drug-treated patients. Although the causes of death were varied, most of the deaths appeared to be either cardiovascular (e.g., heart failure, sudden death) or infectious (e.g., pneumonia) in nature [see WARNINGS AND PRECAUTIONS, Special Populations, Use in Elderly Patients with Dementia].
Taro-Lurasidone should be used with caution in elderly patients and patients with known cardiovascular disease (e.g., heart failure, history of myocardial infarction, ischemia, or conduction abnormalities), cerebrovascular disease, or conditions that predispose the patient to hypotension (e.g., dehydration, hypovolemia, and treatment with antihypertensive medications). Monitoring of orthostatic vital signs should be considered in patients who are vulnerable to hypotension.
Assessment of orthostatic hypotension was defined by vital sign changes (≥20 mmHg decrease in systolic blood pressure and ≥10 bpm increase in pulse from sitting to standing or supine to standing positions).
Schizophrenia
Adults
The incidence of orthostatic hypotension and syncope reported as adverse events from short-term, placebo-controlled schizophrenia studies was (lurasidone hydrochloride tablet incidence; placebo incidence): orthostatic hypotension (5/1508 or 0.3% lurasidone hydrochloride tablets; 1/708 or 0.1% placebo) and syncope (2/1508 or 0.1% lurasidone hydrochloride tablets; 0/708 or 0% placebo). In short-term clinical trials orthostatic hypotension, as assessed by vital signs and occurring at any post-baseline assessment, occurred with a frequency of 4.2% with lurasidone hydrochloride tablets 40 mg, 3.3% with lurasidone hydrochloride tablets 80 mg, 3.7% with lurasidone hydrochloride tablets 120 mg, and 2.5% with lurasidone hydrochloride tablets 160 mg compared to 1.6% with placebo.
Adolescents
The incidence of orthostatic hypotension reported as adverse events from the short-term (6 week), placebo-controlled adolescent schizophrenia study was 0.5% (1/214) in lurasidone hydrochloride tablet-treated patients and 0% (0/112) with placebo. No syncope event was reported. Orthostatic hypotension, as assessed by vital signs, occurred with a frequency of 0% with lurasidone hydrochloride tablets 40 mg and 2.9% with lurasidone hydrochloride tablets 80 mg, compared to 1.8% with placebo.
Bipolar Depression
Adults
Monotherapy
In the short-term, placebo-controlled monotherapy study, there were no reported adverse events of orthostatic hypotension or syncope. Orthostatic hypotension, as assessed by vital signs and occurring at any post-baseline assessment, occurred with a frequency of 6.8% in the lurasidone hydrochloride tablets 20-60 mg and 4.3% in the lurasidone hydrochloride tablets 80-120 mg flexible-dose groups compared to 1.2% with placebo.
Adjunctive Therapy
In the short-term, flexible-dose, placebo-controlled adjunctive therapy studies, there were no reported adverse events of orthostatic hypotension or syncope. Orthostatic hypotension, as assessed by vital signs and occurring at any post-baseline assessment, occurred with a frequency of 4.5% with lurasidone hydrochloride tablets 20-120 mg compared to 4.9% with placebo.
Children and Adolescents
No incidences of orthostatic hypotension were reported as adverse events from the children and adolescents short-term, placebo-controlled bipolar depression study. No syncope event was reported in lurasidone hydrochloride tablet-treated subjects. Orthostatic hypotension, as assessed by vital signs and occurring at any post-baseline assessment, occurred with a frequency of 1.1% with lurasidone hydrochloride tablets 20 to 80 mg/day, compared to 0.6% with placebo.
QT Interval
Thorough QT Study: The effects of lurasidone hydrochloride tablets on the QT/QTc interval were evaluated in a dedicated QT study. The trial involved lurasidone hydrochloride tablet doses of 120 and 600 mg once daily and ziprasidone (80 mg twice daily) as a positive control. The study was conducted in 87 clinically stable patients with schizophrenia. ECG data were collected over an 8 hour time period on the baseline day (Day 0) and on Day 11 of the double-blind treatment period. Statistically significant increases from baseline in the QTcF (N=63) interval were observed from 1 to 8 hour post-dosing with lurasidone 120 mg, lurasidone 600 mg, and ziprasidone 160 mg. The maximum mean increases in QTcF from baseline were 11.6 msec for lurasidone 120 mg (N=22), 9.9 msec for lurasidone 600 mg (N=18), and 21.1 msec for ziprasidone (N=23). There was no apparent dose (exposure)-response relationship in this study. No patients treated with lurasidone hydrochloride experienced tablet QTc increases ≥60 msec from baseline, or a QTc of ≥500 msec.
Phase 2/3 clinical studies: In the short-term, placebo-controlled trials, a single 12-lead ECG was recorded at screening, at baseline in most studies, and at one or more days during the double-blind period, at either pre-dose or at a single post-dosing time point. In the short-term, placebo-controlled trials, no post-baseline QTc prolongations exceeding 500 msec were reported in patients treated with lurasidone hydrochloride tablets or placebo, or any of the active comparators.
The use of Taro-Lurasidone should be avoided in combination with drugs known to prolong QTc including Class 1A antiarrhythmics (e.g., quinidine, procainamide) or Class 3 antiarrhythmics (e.g., amiodarone, sotalol), antipsychotic medications (e.g., ziprasidone, chlorpromazine, thioridazine), and antibiotics (e.g., gatifloxacin, moxifloxacin). Taro-Lurasidone should also be avoided in patients with a history of cardiac arrhythmias and in other circumstances that may increase the risk of the occurrence of torsade de pointes and/or sudden death in association with the use of drugs that prolong the QTc interval, including bradycardia, hypokalemia, or hypomagnesemia; and presence of congenital prolongation of the QT interval.
Venous Thromboembolism
See also WARNINGS AND PRECAUTIONS, Hematologic, Venous Thromboembolism.
Dependence/Tolerance
Lurasidone hydrochloride tablets have not been systematically studied in humans for its potential for abuse or physical dependence or its ability to induce tolerance. While clinical studies with lurasidone hydrochloride tablets did not reveal any tendency for drug-seeking behaviour, these observations were not systematic and it is not possible to predict the extent to which a CNS-active drug will be misused, diverted, and/or abused once it is marketed. Patients should be evaluated carefully for a history of drug abuse, and such patients should be observed carefully for signs of Taro-Lurasidone misuse or abuse (e.g., development of tolerance, drug-seeking behaviour, increases in dose).
Endocrine and Metabolism
Hyperglycemia and Diabetes Mellitus [see ADVERSE REACTIONS]
Hyperglycemia, in some cases extreme and associated with ketoacidosis or hyperosmolar coma or death, has been reported in patients treated with atypical antipsychotics. These cases were, for the most part, seen in post-marketing clinical use and epidemiologic studies, and not in clinical trials. Diabetic ketoacidosis (DKA) has occurred in patients treated with antipsychotics with no reported history of hyperglycemia.
In clinical trials, hyperglycemia or exacerbation of pre-existing diabetes has occasionally been reported during treatment with lurasidone hydrochloride tablets.
Assessment of the relationship between atypical antipsychotic use and glucose abnormalities is complicated by the possibility of an increased background risk of diabetes mellitus in patients with schizophrenia and the increasing incidence of diabetes mellitus in the general population. Given these confounders, the relationship between atypical antipsychotic use and hyperglycemia-related adverse events is not completely understood. However, epidemiological studies, which did not include lurasidone hydrochloride tablets, suggest an increased risk of treatment-emergent hyperglycemia-related adverse events in patients treated with the atypical antipsychotics. Because lurasidone hydrochloride tablets were not marketed at the time these studies were performed, it is not known if Taro-Lurasidone is associated with this increased risk. Precise risk estimates for hyperglycemia-related adverse events in patients treated with atypical antipsychotics are not available.
Patients should have baseline and periodic monitoring of blood glucose and body weight. Any patient treated with atypical antipsychotics should be monitored for symptoms of hyperglycemia including polydipsia, polyuria, polyphagia, and weakness. Patients who develop symptoms of hyperglycemia during treatment with atypical antipsychotics should undergo fasting blood glucose testing. In some cases, hyperglycemia has resolved when the atypical antipsychotic was discontinued; however, some patients required continuation of anti-diabetic treatment despite discontinuation of the suspect drug. Patients with risk factors for diabetes mellitus (e.g., obesity, family history of diabetes) who are starting treatment with atypical antipsychotics should undergo fasting blood glucose testing at the beginning of treatment and periodically during treatment. Patients with an established diagnosis of diabetes mellitus who are started on atypical antipsychotics should be monitored regularly for worsening of glucose control.
Hyperprolactinemia
As with other drugs that antagonize dopamine D2 receptors, Taro-Lurasidone can elevate prolactin levels [see ADVERSE REACTIONS].
Hyperprolactinemia may suppress hypothalamic GnRH, resulting in reduced pituitary gonadotrophin secretion. This, in turn, may inhibit reproductive function by impairing gonadal steroidogenesis in both female and male patients. Galactorrhea, amenorrhea, gynecomastia, and impotence have been reported with prolactin-elevating compounds. Long-standing hyperprolactinemia when associated with hypogonadism may lead to decreased bone mineral density in both female and male patients.
Tissue culture experiments indicate that approximately one-third of human breast cancers are prolactin dependent in vitro, a factor of potential importance if the prescription of these drugs is considered in a patient with previously detected breast cancer. As is common with compounds which increase prolactin release, an increase in mammary gland neoplasia was observed in a lurasidone hydrochloride tablet carcinogenicity study conducted in rats and mice [see TOXICOLOGY]. The physiological differences between rats and humans with regard to prolactin make the clinical significance of these findings unclear. To date, neither clinical nor epidemiological studies have shown an association between chronic administration of these drugs and mammary tumorigenesis.
Schizophrenia
Adults
In short-term, placebo-controlled trials in patients with schizophrenia, the proportion of patients with prolactin elevations ≥5X ULN was 2.8% for lurasidone hydrochloride tablet-treated patients versus 1.0% for placebo-treated patients. The proportion of female patients with prolactin elevations ≥5X ULN was 5.7% for lurasidone hydrochloride tablet-treated patients versus 2.0% for placebo-treated female patients. The proportion of male patients with prolactin elevations ≥5X ULN was 1.6% versus 0.6% for placebo-treated male patients.
Adolescents
The proportion of patients with prolactin elevations ≥5X ULN was 0.5% for lurasidone hydrochloride tablet-treated patients (1.0% for 40 mg and 0% for 80 mg dose) versus 1.0% for placebo-treated patients. The proportion of female patients with prolactin elevations ≥5X ULN was 1.3% for lurasidone hydrochloride tablet-treated patients (2.4% for 40 mg and 0% for 80 mg dose) versus 0% for placebo-treated female patients. The proportion of male patients with prolactin elevations ≥5X ULN was 0% for lurasidone hydrochloride tablet-treated patients versus 1.6% for placebo-treated male patients.
Bipolar Depression
Adults
Monotherapy
In the short-term, placebo-controlled monotherapy study, the proportion of patients with prolactin elevations ≥5X ULN was 0.4% for lurasidone hydrochloride tablet-treated patients versus 0.0% for placebo-treated patients. The proportion of female patients with prolactin elevations ≥5X ULN was 0.6% for lurasidone hydrochloride tablet-treated patients versus 0% for placebo-treated female patients. There were no prolactin elevations ≥5X ULN in male patients
Adjunctive Therapy
In the short-term, flexible-dose, placebo-controlled adjunctive therapy studies, there were no patients with prolactin elevations ≥5X ULN.
Children and Adolescents
In the children and adolescents short-term, placebo-controlled bipolar depression study, the proportion of patients with prolactin elevations ≥5X ULN was 0% for lurasidone hydrochloride tablet-treated patients versus 0.6% for placebo-treated patients. The proportion of female patients with prolactin elevations ≥5X ULN was 0% for lurasidone hydrochloride tablet-treated patients versus 1.3% for placebo-treated female patients. The proportion of male patients with prolactin elevations ≥5X ULN was 0% for lurasidone hydrochloride tablet-treated patients versus 0% for placebo-treated male patients.
The median change from baseline to endpoint in prolactin levels for lurasidone hydrochloride tablet-treated patients was +1.10 ng/mL and was +0.50 ng/mL for placebo-treated patients. For lurasidone hydrochloride tablet-treated patients, the median change from baseline to endpoint for males was +0.85 ng/mL and for females was +2.50 ng/mL [See ADVERSE REACTIONS, Abnormal Hematologic and Clinical Chemistry Findings, Hyperprolactinemia].
Weight Gain
Schizophrenia
Adults
In pooled short-term (6-week) clinical trials, the mean change in weight was a 0.43 kg increase for lurasidone hydrochloride tablet-treated patients compared to a 0.02 kg decrease for placebo-treated patients. The proportion of patients with a ≥7% increase in body weight (at Endpoint) was 4.8% for lurasidone hydrochloride tablet-treated patients versus 3.3% for placebo-treated patients.
Adolescents
In the short-term (6 week), placebo-controlled adolescent schizophrenia study, the mean weight gain was 0.5 kg for lurasidone hydrochloride tablet-treated patients (0.3 kg for 40 mg and 0.7 kg for 80 mg dose) compared to 0.2 kg for placebo-treated patients. The proportion of patients with a ≥ 7% increase in body weight (at Endpoint) was 2.3% for lurasidone hydrochloride tablet-treated patients (2.8% for 40 mg and 1.9% for 80 mg dose) versus 4.5% for placebo-treated patients.
Bipolar Depression
Adults
Monotherapy
In the short-term, placebo-controlled monotherapy study, the mean weight gain was 0.29 kg for lurasidone hydrochloride tablet-treated patients compared to -0.04 kg for placebo-treated patients. The proportion of patients with a ≥ 7% increase in body weight (at Endpoint) was 2.4% for lurasidone hydrochloride tablet-treated patients versus 0.7% for placebo-treated patients.
Adjunctive Therapy
In the short-term, flexible-dose, placebo-controlled adjunctive therapy studies, the mean weight gain was 0.11 kg for lurasidone hydrochloride tablet-treated patients compared to 0.16 kg for placebo-treated patients. The proportion of patients with a ≥ 7% increase in body weight (at Endpoint) was 3.1% for lurasidone hydrochloride tablet-treated patients versus 0.3% for placebo-treated patients.
Children and Adolescents
In the children and adolescents short-term, placebo-controlled bipolar depression study, 7% of lurasidone hydrochloride tablet-treated patients reported weight gain as an adverse event compared to
2% of placebo-treated patients. The mean weight gain was 0.7 kg for lurasidone hydrochloride tablet-treated patients compared to 0.5 kg for placebo-treated patients. The proportion of patients with a ≥ 7% increase in body weight (at Endpoint) was 4.0% for lurasidone hydrochloride tablet-treated patients versus 5.3% for placebo-treated patients.
Gastrointestinal
Antiemetic Effect
Drugs that have dopamine antagonist effects may have an antiemetic effect. Such an effect may mask signs of toxicity due to overdosage of other drugs, or may mask symptoms of disease such as brain tumour or intestinal obstruction.
Genitourinary
Rare cases of priapism have been reported with antipsychotic use, such as lurasidone hydrochloride tablets. This adverse reaction is generally not found to be dose-dependent or correlated with the duration of treatment.
Hematologic
Leukopenia, Neutropenia, and Agranulocytosis
Neutropenia, granulocytopenia, and agranulocytosis have been reported during antipsychotic use. Therefore, it is recommended that patients have their complete blood count (CBC) tested prior to starting Taro-Lurasidone and then periodically throughout treatment.
Possible risk factors for leukopenia/neutropenia include pre-existing low white blood cell count (WBC) and history of drug induced leukopenia/neutropenia. Patients with a pre-existing low WBC or a history of drug induced leukopenia/neutropenia should have their complete blood count (CBC) monitored frequently during the first few months of therapy and Taro-Lurasidone should be discontinued at the first sign of decline in WBC, in the absence of other causative factors. Patients with neutropenia should be carefully monitored for fever or other symptoms or signs of infection and treated promptly if such symptoms or signs occur. Patients with severe neutropenia (absolute neutrophil count <1 x 10⁹/L) should discontinue Taro-Lurasidone and have their WBC followed until recovery.
Venous Thromboembolism
Venous thromboembolism (VTE), including fatal pulmonary embolism, has been reported with antipsychotic drugs, including lurasidone hydrochloride tablets, in case reports and/or observational studies. When prescribing Taro-Lurasidone all potential risk factors for VTE should be identified and preventative measures undertaken.
Hepatic
See WARNINGS AND PRECAUTIONS, Special Populations, Use in Patients with Hepatic Impairment, DOSAGE AND ADMINISTRATION and ACTION AND CLINICAL PHARMACOLOGY.
Immune
Drug Reaction with Eosinophilia and Systemic Symptoms (DRESS)
Post market cases of DRESS have been reported in association with similar atypical antipsychotic drugs within the class.
Neurologic
Neuroleptic Malignant Syndrome
A potentially fatal symptom complex sometimes referred to as Neuroleptic Malignant Syndrome (NMS) has been reported in association with administration of antipsychotic drugs, including lurasidone hydrochloride tablets [see ADVERSE REACTIONS].
Clinical manifestations of NMS are hyperpyrexia, muscle rigidity, altered mental status, and evidence of autonomic instability (irregular pulse or blood pressure, tachycardia, diaphoresis, and cardiac dysrhythmia). Additional signs may include elevated creatine phosphokinase, myoglobinuria (rhabdomyolysis), and acute renal failure.
In arriving at a diagnosis, it is important to identify cases where the clinical presentation includes both serious medical illness (e.g., pneumonia, systemic infection) and untreated or inadequately treated extrapyramidal signs and symptoms (EPS). Other important considerations in the differential diagnosis include central anticholinergic toxicity, heat stroke, drug fever, and primary central nervous system pathology.
The management of NMS should include: 1) immediate discontinuation of all antipsychotic drugs, including Taro-Lurasidone, and other drugs not essential to concurrent therapy; 2) intensive symptomatic treatment and medical monitoring; and 3) treatment of any concomitant serious medical problems for which specific treatments are available. There is no general agreement about specific pharmacological treatment regimens for uncomplicated NMS.
If a patient requires antipsychotic drug treatment after recovery from NMS, the potential reintroduction of drug therapy should be carefully considered. The patient should be carefully monitored, since recurrences of NMS have been reported.
Tardive Dyskinesia [see ADVERSE REACTIONS]
Tardive dyskinesia, a syndrome consisting of potentially irreversible, involuntary, dyskinetic movements, may develop in patients treated with antipsychotic drugs. Although the prevalence of the syndrome appears to be highest among the elderly, especially elderly women, it is impossible to rely upon prevalence estimates to predict, at the inception of antipsychotic treatment, which patients are likely to develop the syndrome. Whether antipsychotic drug products differ in their potential to cause tardive dyskinesia is unknown.
The risk of developing tardive dyskinesia and the likelihood that it will become irreversible are believed to increase as the duration of treatment and the total cumulative dose of antipsychotic drugs administered to the patient increase. However, the syndrome can develop, although much less commonly, after relatively brief treatment periods at low doses.
There is no known treatment for established cases of tardive dyskinesia, although the syndrome may remit, partially or completely, if antipsychotic treatment is withdrawn. Antipsychotic treatment, itself, however, may suppress (or partially suppress) the signs and symptoms of the syndrome and thereby may possibly mask the underlying process. The effect that symptomatic suppression has upon the long-term course of the syndrome is unknown.
Given these considerations, Taro-Lurasidone should be prescribed in a manner that is most likely to minimize the occurrence of tardive dyskinesia. Chronic antipsychotic treatment should generally be reserved for patients who suffer from a chronic illness that 1) is known to respond to antipsychotic drugs, and 2) for whom alternative, equally effective, but potentially less harmful treatments are not available or appropriate. In patients who do require chronic treatment, the smallest dose and the shortest duration of treatment producing a satisfactory clinical response should be sought. The need for continued treatment should be reassessed periodically.
If signs and symptoms of tardive dyskinesia appear in a patient on Taro-Lurasidone, drug discontinuation should be considered. However, some patients may require treatment with Taro-Lurasidone despite the presence of the syndrome.
Seizures
As with other antipsychotic drugs, Taro-Lurasidone should be used cautiously in patients with a history of seizures or with conditions that lower the seizure threshold, e.g., Alzheimer’s dementia [see ADVERSE REACTIONS]. Conditions that lower the seizure threshold may be more prevalent in patients 65 years or older.
Potential for Cognitive and Motor Impairment
Taro-Lurasidone, like other antipsychotics, has the potential to impair judgement, thinking, or motor skills [see ADVERSE REACTIONS]. Somnolence is a commonly reported adverse event in patients treated with lurasidone hydrochloride tablets.
Patients should be cautioned about operating hazardous machinery, including motor vehicles, until they are reasonably certain that therapy with Taro-Lurasidone does not affect them adversely.
Schizophrenia
Adults
In short-term, placebo-controlled schizophrenia studies, somnolence was reported in 17% of patients treated with lurasidone hydrochloride tablet doses from 20 mg to 160 mg/day.
Adolescents
In a short-term (6 week), placebo-controlled adolescent schizophrenia study, somnolence was reported by 14.5% (31/214) of patients treated with lurasidone hydrochloride tablets (15.5% lurasidone hydrochloride tablets 40 mg and 13.5% lurasidone hydrochloride tablets 80 mg/day) compared to 7.1% (8/112) of placebo patients.
Bipolar Depression
Adults
Monotherapy
In the short-term, placebo-controlled monotherapy study, somnolence was reported by 7.3% (12/164) and 13.8% (23/167) of patients in the lurasidone hydrochloride tablets 20-60 mg and lurasidone hydrochloride tablets 80-120 mg flexible-dose groups, respectively, compared to 6.5% (11/168) of placebo patients.
Adjunctive Therapy
In the short-term, flexible-dose, placebo-controlled adjunctive therapy studies, somnolence was reported by 11.4% (41/360) of patients treated with lurasidone hydrochloride tablets 20-120 mg compared to 5.1% (17/334) of placebo patients.
Children and Adolescents
In the children and adolescents short-term, placebo-controlled bipolar depression study, somnolence was reported by 11.4% (20/175) of patients treated with lurasidone hydrochloride tablets 20 to 80 mg/day compared to 5.8% (10/172) of placebo-treated patients.
Falls
Taro-Lurasidone may cause somnolence, postural hypotension, motor and sensory instability, which may lead to falls and, consequently, fractures or other injuries. For patients with diseases, conditions, or medications that could exacerbate these effects, complete fall risk assessments when initiating antipsychotic treatment and recurrently for patients on long-term antipsychotic therapy.
Psychiatric
Suicide [see ADVERSE REACTIONS]
Suicide/suicidal thoughts or clinical worsening: Depressive episodes are associated with an increased risk of suicidal thoughts, self-harm and suicide (suicide-related events). This risk persists until significant remission of depression occurs. As improvement may not occur during the first few weeks or more of treatment, patients should be closely monitored until such improvement occurs. It is general clinical experience that the risk of suicide may increase in the early stages of recovery. In addition to depressive episodes associated with bipolar disorder, depression may be co-morbid with schizophrenia.
Schizophrenia is also associated with an increased risk of suicide-related events, and thus close supervision and appropriate clinical management of high risk patients should accompany drug therapy.
In a short-term (6 week), placebo-controlled adolescent schizophrenia study, the incidence of treatment-emergent suicidal ideation was 3.3% (7/213) for lurasidone hydrochloride tablet-treated patients compared to 4.5% (5/112) on placebo. No suicide attempts or completed suicides were reported in this study.
Patients with a history of suicide-related events are also known to be at a greater risk of suicidal thoughts or suicide attempts, and should receive careful monitoring during treatment.
Prescriptions for Taro-Lurasidone should be written for the smallest quantity of tablets consistent with good patient management in order to reduce the risk of overdose.
Renal
See WARNINGS AND PRECAUTIONS, Special Populations, Use in Patients with Renal Impairment, DOSAGE AND ADMINISTRATION and ACTION AND CLINICAL PHARMACOLOGY.
Special Populations
Pregnant Women
Teratogenic Effects: There are no adequate and well-controlled studies of lurasidone hydrochloride tablets in pregnant woman. Lurasidone was not teratogenic in rats and rabbits [see also TOXICOLOGY, Reproductive and Developmental Toxicity].
Non-Teratogenic Effects: Neonates exposed to antipsychotic drugs during the third trimester of pregnancy are at risk for extrapyramidal and/or withdrawal symptoms following delivery. There have been reports of agitation, hypertonia, hypotonia, tremor, somnolence, respiratory distress, and feeding disorder in these neonates. These complications have varied in severity; while in some cases symptoms have been self-limited, in other cases neonates have required intensive care unit support and prolonged hospitalization.
Patients should be advised to notify their physician if they become pregnant or intend to become pregnant during treatment with Taro-Lurasidone. Taro-Lurasidone should be used during pregnancy only if the potential benefit justifies the potential risk to the fetus.
Labour and Delivery
The effect of lurasidone hydrochloride tablets on labour and delivery in humans is unknown.
Nursing Women
Lurasidone hydrochloride was excreted in milk of rats during lactation. It is not known whether lurasidone hydrochloride or its metabolites are excreted in human milk. It is recommended that women receiving Taro-Lurasidone should not breast-feed.
Pediatrics (<18 years of age)
When prescribing to adolescents with schizophrenia (15-17 years of age) or adolescents with depressive episodes associated with bipolar I disorder (13 -17 years of age), clinicians must take into account the safety concerns associated with all antipsychotic drugs which include: extrapyramidal effects, hyperglycemia, weight gain, and hyperlipidemia, which can be more frequent or more severe in this patient population than in adults [see WARNINGS AND PRECAUTIONS and ADVERSE
REACTIONS]. Taro-Lurasidone should only be prescribed to adolescents with schizophrenia or bipolar I disorder by clinicians who are experienced in the diagnosis and treatment of adolescents with psychiatric illness and who are experienced in the early detection and management of the above-mentioned safety issues associated with this class of drugs.
Weight gain has been observed with atypical antipsychotic use in pediatric and adolescent patient populations. Independent of any drug-specific effects, weight gain can be associated with adverse changes in other metabolic parameters (e.g., glucose and lipid metabolism).
Abnormal childhood weight and metabolic status can have adverse effects on cardiovascular outcomes in adulthood. Weight gain and adverse effects on other metabolic parameters associated with atypical antipsychotics can be more frequent or more severe in pediatric and adolescent patients than in the adult patients.
The long-term safety, including cardiometabolic effects and effects on growth, maturation and behavioural development in patients under 18 years of age has not been systematically evaluated.
Schizophrenia
The safety and efficacy of lurasidone hydrochloride tablets in the treatment of manifestations of schizophrenia in adolescents (15 to 17 years) were established in a 6-week, placebo-controlled clinical study in 326 adolescent patients [see DOSAGE AND ADMINISTRATION, ADVERSE REACTIONS, and CLINICAL TRIALS].
The following adverse events reported in the study in adolescents with schizophrenia were reported at a greater incidence rate compared to the adult schizophrenia studies, or with a greater differential over placebo: Nausea (differential over placebo 10.9% for all doses in adolescents versus 5% average for all doses in adult studies), vomiting (differential over placebo 5.7% for all doses in adolescents versus 2% average for all doses in adult studies), dizziness (differential over placebo 3.8% for all doses in adolescents versus 2% average for all doses in adult studies), and diarrhea (differential over placebo 1.8% for all doses in adolescents; all cases resolved within a few days without dose adjustment or discontinuation) [see ADVERSE REACTIONS].
Irritability Associated with Autistic Disorder
Efficacy was not demonstrated in a 6-week study evaluating lurasidone hydrochloride tablets 20 mg/day and 60 mg/day for the treatment of pediatric patients 6 to 17 years of age with irritability associated with autistic disorder.
Bipolar Depression
The safety and efficacy of lurasidone hydrochloride tablets 20 to 80 mg/day for the treatment of bipolar depression in adolescents (13 to 17 years) was established in a 6-week, placebo-controlled clinical study in 343 children and adolescents (10-17 years). Taro-Lurasidone is not indicated for the treatment of depressive episodes in bipolar I disorder in patients less than 13 years of age due to insufficient safety and efficacy data [see ADVERSE REACTIONS, DOSAGE AND ADMINISTRATION and CLINICAL TRIALS].
The following adverse events reported in the study in children and adolescents with bipolar depression were reported at a greater incidence rate compared to the adult bipolar monotherapy studies, or with a greater differential over placebo: Nausea (differential over placebo 10.2% in children and adolescents versus 6.2% average for all doses in adult monotherapy studies), vomiting (differential over placebo 2.8% in children and adolescents versus 2.4% average for all doses in adult monotherapy studies), somnolence (differential over placebo 5.6% in children and adolescents versus 4.1% average for all doses in adult monotherapy studies), weight increase (differential over placebo 5.2% in children and adolescents), abdominal pain upper (differential over placebo 1.1% in children and adolescents), insomnia (differential over placebo 2.8% in children and adolescents), dizziness (differential over placebo 1% in children and adolescents).
Geriatrics (≥65 years of age)
Clinical studies of lurasidone hydrochloride tablets did not include sufficient numbers of patients aged 65 and older to determine whether or not they respond differently than younger patients. Caution should, thus, be exercised with the use of Taro-Lurasidone in the elderly patient, recognizing the more frequent hepatic, renal, central nervous system and cardiovascular dysfunctions, and more frequent use of concomitant medications in this population [see also WARNINGS AND PRECAUTIONS, Hepatic, Renal, DOSAGE AND ADMINISTRATION and DRUG INTERACTIONS].
Use in Geriatric Patients with Dementia
Overall Mortality: Elderly patients with dementia treated with atypical antipsychotic drugs have an increased mortality compared to placebo in a meta-analysis of 13 controlled trials of various atypical antipsychotic drugs. Taro-Lurasidone is not indicated in elderly patients with dementia (e.g., dementia-related psychosis) [see Boxed Warning].
Cerebrovascular Adverse Reactions, including Stroke: In placebo-controlled trials with some atypical antipsychotics in elderly subjects with dementia, there was a higher incidence of cerebrovascular adverse reactions (cerebrovascular accidents and transient ischemic attacks), including fatalities, compared to placebo-treated subjects. Taro-Lurasidone is not approved for the treatment of patients with dementia (e.g., dementia-related psychosis) [see Boxed Warning].
Dysphagia: Esophageal dysmotility and aspiration have been associated with antipsychotic drug use, including lurasidone hydrochloride tablets. Aspiration pneumonia is a common cause of morbidity and mortality in elderly patients, in particular those with advanced Alzheimer’s dementia. Taro-Lurasidone is not indicated for the treatment of dementia-related psychosis, and should not be used in patients at risk for aspiration pneumonia.
Use in Patients with Hepatic Impairment
Caution should be exercised when starting Taro-Lurasidone in patients with hepatic impairment. The recommended starting dose is 20 mg. Patients should be treated with the lowest effective dose that provides optimal clinical response and tolerability, which is expected to be 20-40 mg once daily for most patients with moderate or severe hepatic impairment (Child Pugh Class B and C). The dose should not exceed 40 mg/day in patients with severe hepatic impairment, and 80 mg/day in patients with moderate hepatic impairment [see DOSAGE AND ADMINISTRATION and ACTION AND CLINICAL PHARMACOLOGY].
Use in Patients with Renal Impairment
Caution should be exercised when starting Taro-Lurasidone in patients with renal impairment. The recommended starting dose is 20 mg. Patients should be treated with the lowest effective dose that provides optimal clinical response and tolerability, which is expected to be 20-40 mg once daily for most patients with moderate and severe renal impairment (Clcr ≥10 mL/min to <50 mL/min). The dose should not exceed 80 mg/day in patients with moderate and severe renal impairment [see DOSAGE AND ADMINISTRATION and ACTION AND CLINICAL PHARMACOLOGY].
Use in Patients with Concomitant Illness
Clinical experience with lurasidone hydrochloride tablets in patients with certain concomitant systemic illnesses is limited. Lurasidone hydrochloride tablets have not been evaluated or used to any appreciable extent in patients with a recent history of myocardial infarction or unstable heart disease. Patients with these diagnoses were excluded from premarketing clinical studies.
ADVERSE REACTIONS
Adverse Drug Reaction Overview
The information below is derived from an integrated clinical study database for lurasidone hydrochloride tablets consisting of 3799 adult patients exposed to one or more doses of lurasidone hydrochloride tablets for the treatment of schizophrenia and bipolar depression in placebo-controlled studies. This experience corresponds to a total experience of 1250.9 patient-years. A total of 1106 lurasidone hydrochloride tablet-treated patients had at least 24 weeks and 371 lurasidone hydrochloride tablet-treated patients had at least 52 weeks of exposure.
The information below is also derived from a short-term (6 week), placebo-controlled adolescent study for schizophrenia in which lurasidone hydrochloride tablets was administered at daily doses of 40 or 80 mg to 214 adolescent patients (13-17 years) and a children and adolescents short-term, placebo-controlled study for bipolar depression in which lurasidone hydrochloride tablets were administered at daily doses ranging from 20 to 80 mg to 175 child and adolescent patients (10 to 17 years). Taro-Lurasidone is not indicated for the treatment of schizophrenia in adolescents less than 15 years of age or for the treatment of depressive episodes in bipolar I disorder in patients less than 13 years of age due to insufficient safety and efficacy data [see CLINICAL TRIALS].
Adverse events during exposure to study treatment were obtained by general inquiry and voluntarily reported adverse experiences, as well as results from physical examinations, vital signs, ECGs, weights, and laboratory investigations. Adverse experiences were recorded by clinical investigators using their own terminology. In order to provide a meaningful estimate of the proportion of individuals experiencing adverse events, events were grouped in standardized categories using MedDRA terminology.
The stated frequencies of adverse reactions represent the proportion of individuals who experienced at least once, a treatment-emergent adverse event of the type listed. Treatment-emergent adverse events were defined as adverse experiences, which started or worsened on or after the date of the first dose through seven days after study medication discontinuation. There was no attempt to use investigator causality assessments; i.e., all events meeting the defined criteria, regardless of investigator causality are included. It is important to emphasize that, although the reactions occurred during treatment with lurasidone hydrochloride tablets, they were not necessarily caused by it. The label should be read in its entirety to gain an understanding of the safety profile of Taro-Lurasidone.
Clinical Trial Adverse Drug Reactions
Because clinical trials are conducted under very specific conditions, the adverse reaction rates observed in the clinical trials may not reflect the rates observed in practice and should not be compared to the rates in the clinical trials of another drug. Adverse drug reaction information from clinical trials is useful for identifying drug-related adverse events and for approximating rates.
Short-Term, Placebo-Controlled Trials of Patients with Schizophrenia
Adults
The following findings are based on the 7 short-term, placebo-controlled premarketing studies for schizophrenia in which lurasidone hydrochloride tablets were administered at daily doses ranging from 20 to 160 mg (n=1508) for up to 6 weeks [see also CLINICAL TRIALS].
Commonly Observed Treatment-emergent Adverse Events: The most common adverse events (incidence ≥5% in all pooled lurasidone patients in the short-term trials and at least twice the rate of placebo) in patients treated with lurasidone hydrochloride tablets were: nausea, somnolence, akathisia, and parkinsonism (see Table 1).
Treatment-emergent Adverse Events Associated with Discontinuation of Treatment: A total of 9.5% (143/1508) of lurasidone hydrochloride tablet-treated patients and 9.3% (66/708) of placebo-treated patients discontinued due to adverse events. There were no adverse events associated with discontinuation in subjects treated with lurasidone hydrochloride tablets that were at least 2% and at least twice the placebo rate. The most frequent adverse events leading to discontinuation in lurasidone hydrochloride tablet-treated patients were psychiatric events related to worsening of schizophrenia (3.4%) and EPS events (1.9%). Of the EPS events, akathisia was 1.4%.
Treatment-emergent Adverse Events Occurring at an Incidence of 2% or More in Lurasidone Hydrochloride Tablet-treated Patients: Adverse events associated with the use of lurasidone hydrochloride tablets by dose group (pooled from different studies for the 40 mg, 80 mg, and 120 mg doses) and all doses pooled (incidence of 2% or greater, rounded to the nearest percent, and lurasidone hydrochloride tablet incidence greater than placebo in all doses pooled) that occurred during acute therapy (up to 6-weeks in patients with schizophrenia) are shown in Table 1.
Table 1: Treatment-emergent Adverse Events in 2% or More of Lurasidone Hydrochloride Tablet-treated Adult Patients and that Occurred at Greater Incidence than in the Placebo-treated Adult Patients in Short-term Schizophrenia Studies
| Percentage of Adult Patients Reporting Event | |||||||
| Body System or Organ Class | Placebo (N=708) | Lurasidone Hydro-chloride Tablet 20 mg/d (N=71) | Lurasidone Hydro-chloride Tablet 40 mg/d (N=487) | Lurasidone Hydro-chloride Tablet 80 mg/d (N=538) | Lurasidone Hydro-chloride Tablet 120 mg/d (N=291) | Lurasidone Hydro-chloride Tablet 160 mg/d (N=121) | Lurasidone Hydro-chloride Tablet (N=1508) |
| Gastrointestinal Disorders | |||||||
| Nausea | 5% | 11% | 10% | 9% | 13% | 7% | 10% |
| Vomiting | 6% | 7% | 6% | 9% | 9% | 7% | 8% |
| Dyspepsia | 5% | 11% | 6% | 5% | 8% | 6% | 6% |
| Salivary Hypersecretion | <1% | 1% | 1% | 2% | 4% | 2% | 2% |
| Musculoskeletal and Connective Tissue Disorders | |||||||
| Back Pain | 2% | 0% | 4% | 3% | 4% | 0% | 3% |
| Nervous System Disorders | |||||||
| Somnolence* | 7% | 15% | 16% | 15% | 26% | 8% | 17% |
| Akathisia | 3% | 6% | 11% | 12% | 22% | 7% | 13% |
| Parkinsonism** | 5% | 6% | 9% | 8% | 17% | 11% | 10% |
| Dizziness | 2% | 6% | 4% | 4% | 5% | 6% | 4% |
| Dystonia*** | <1% | 0% | 3% | 4% | 7% | 2% | 4% |
| Psychiatric Disorders | |||||||
| Insomnia | 8% | 8% | 10% | 11% | 9% | 7% | 10% |
| Agitation | 4% | 10% | 7% | 3% | 6% | 5% | 5% |
| Anxiety | 4% | 3% | 6% | 4% | 7% | 3% | 5% |
| Restlessness | 1% | 1% | 3% | 1% | 3% | 2% | 2% |
Note: Figures rounded to the nearest integer
* Somnolence includes adverse event terms: hypersomnia, hypersomnolence, sedation, and somnolence
** Parkinsonism includes adverse event terms: bradykinesia, cogwheel rigidity, drooling, extrapyramidal disorder, hypokinesia, muscle rigidity, parkinsonism, psychomotor retardation, and tremor
*** Dystonia includes adverse event terms: dystonia, oculogyric crisis, oromandibular dystonia, tongue spasm, torticollis, and trismus
Adolescents
The following findings are based on the short-term (6 week), placebo-controlled adolescent study for schizophrenia in which lurasidone hydrochloride tablets were administered at daily doses of 40 or 80 mg (n=214).
Commonly Observed Adverse Reactions: The most common adverse reactions (incidence ≥5% and at least twice the rate of placebo) in adolescent patients (13 to 17 years) treated with lurasidone hydrochloride tablets were somnolence, nausea, akathisia, extrapyramidal symptoms (non-akathisia, 40 mg only), rhinorrhea/rhinitis (80 mg only) and vomiting.
Adverse Reactions Associated with Discontinuation of Treatment: The incidence of discontinuation due to adverse events between lurasidone hydrochloride tablet-treated and placebo-treated adolescent patients (13 to 17 years) was 4% and 8%, respectively (6 (5.5%) subjects receiving lurasidone hydrochloride tablets 40 mg/day and 2 (1.9%) subjects receiving lurasidone hydrochloride tablets 80 mg/day versus 9 (8.0%) subjects receiving placebo). Five of the 6 subjects in the lurasidone hydrochloride tablets 40 mg/day dose group discontinued due to psychiatric disorders (anxiety, homicidal ideation, and suicidal ideation, each in 1 subject, and schizophrenia in 2 subjects) and 1 discontinued due to irritability. Of the 2 subjects in the lurasidone hydrochloride tablets 80 mg/day dose group who discontinued study treatment due to an adverse event, 1 did so due to schizophrenia and the other due to hypersensitivity (allergic reaction).
Adverse Reactions Occurring at an Incidence of 2% or More in Lurasidone Hydrochloride Tablet-Treated Patients: Adverse reactions associated with the use of lurasidone hydrochloride tablets (incidence of 2% or greater, rounded to the nearest percent and lurasidone incidence greater than placebo) that occurred during acute therapy (up to 6-weeks in adolescent patients with schizophrenia) are shown in Table 2.
Table 2: Adverse Reactions in 2% or More of Lurasidone Hydrochloride Tablet-Treated Adolescent Patients and That Occurred at Greater Incidence than in the Placebo-Treated Adolescent Patients in the Short-term Schizophrenia Study
| Percentage of Patients Reporting Reaction | ||||
Body System or Organ Class Dictionary-derived Term | Placebo (N=112) | Lurasidone Hydrochloride Tablet 40 mg/day (N=110) | Lurasidone Hydrochloride Tablet 80 mg/day (N=104) | All Lurasidone Hydrochloride Tablet (N=214) |
| Gastrointestinal Disorders | ||||
| Nausea | 3 | 13 | 14 | 14 |
| Vomiting | 2 | 8 | 6 | 8 |
| Diarrhea | 1 | 3 | 5 | 4 |
| Dry Mouth | 0 | 2 | 3 | 2 |
| Infections and Infestations | ||||
| Viral Infection** | 6 | 11 | 10 | 10 |
| Rhinitis*** | 2 | <1 | 8 | 4 |
| Oropharyngeal pain | 0 | <1 | 3 | 2 |
| Cardiac Disorders | ||||
| Tachycardia | 0 | 0 | 3 | 1 |
| Nervous System Disorders | ||||
| Somnolence* | 7 | 15 | 13 | 15 |
| Akathisia | 2 | 9 | 9 | 9 |
| Dizziness | 1 | 5 | 5 | 5 |
Note: Figures rounded to the nearest integer
* Somnolence includes adverse event terms: hypersomnia, sedation, and somnolence
**Viral Infection includes adverse event terms: nasopharyngitis, influenza, viral infection, upper respiratory tract infection
***Rhinitis incudes adverse event terms: rhinitis, allergic rhinitis, rhinorrhea, and nasal congestion
Short-Term, Placebo-Controlled Trials of Patients with Bipolar Depression
Adults
Monotherapy
The following findings are based on the short-term, placebo-controlled, monotherapy study for bipolar depression (involving lower and higher dose ranges) in which lurasidone hydrochloride tablets were administered at daily doses ranging from 20 to 120 mg (n=331).
Commonly Observed Treatment-emergent Adverse Events: The most common adverse events (incidence ≥ 5% and at least twice the rate of placebo) in patients treated with lurasidone hydrochloride tablets were akathisia and parkinsonism.
Treatment-emergent Adverse Events Associated with Discontinuation of Treatment: A total of 6.0% (20/331) of lurasidone hydrochloride tablet-treated patients and 5.4% (9/168) of placebo-treated patients discontinued due to adverse events. There were no adverse events associated with discontinuation in subjects treated with lurasidone hydrochloride tablets that were at least 2% and at least twice the placebo rate.
Treatment-emergent Adverse Events Occurring at an Incidence of 2% or More in lurasidone hydrochloride tablet-treated Patients: Adverse events associated with the use of lurasidone hydrochloride tablets (incidence of 2% or greater, rounded to the nearest percent and lurasidone hydrochloride tablet incidence greater than placebo) that occurred during acute therapy (up to 6 weeks in patients with bipolar depression) are shown in Table 3.
Table 3: Treatment-emergent Adverse Events in 2% or More of Lurasidone Hydrochloride-treated Adult Patients (Monotherapy) and that Occurred at Greater Incidence than in the Placebo Tablet-treated Patients in a Short-term Bipolar Depression Study
| Percentage of Adult Patients Reporting Reaction | ||||
Body System or Organ Class Dictionary-derived Term | Placebo (N=168) (% ) | Lurasidone Hydrochloride Tablet 20-60 mg/day (N=164) (% ) | Lurasidone Hydrochloride Tablet 80-120 mg/day (N=167) (% ) | All Lurasidone Hydrochloride Tablet (N=331) (% ) |
| Gastrointestinal Disorders | ||||
| Nausea | 8 | 10 | 17 | 14 |
| Dry Mouth | 4 | 6 | 4 | 5 |
| Vomiting | 2 | 2 | 6 | 4 |
| Diarrhea | 2 | 5 | 3 | 4 |
| Infections and Infestations | ||||
| Nasopharyngitis | 1 | 4 | 4 | 4 |
| Influenza | 1 | <1 | 2 | 2 |
| Urinary Tract Infection | <1 | 2 | 1 | 2 |
| Musculoskeletal and Connective Tissue Disorders | ||||
| Back Pain | <1 | 3 | <1 | 2 |
| Nervous System Disorders | ||||
| Extrapyramidal Symptoms* | 2 | 5 | 9 | 7 |
| Somnolence** | 7 | 7 | 14 | 11 |
| Akathisia | 2 | 8 | 11 | 9 |
| Psychiatric Disorders | ||||
| Anxiety | 1 | 4 | 5 | 4 |
Note: Figures rounded to the nearest integer
* Extrapyramidal symptoms includes adverse event terms: bradykinesia, cogwheel rigidity, drooling, dystonia, extrapyramidal disorder, glabellar reflex abnormal, hypokinesia, muscle rigidity, oculogyric crisis, oromandibular dystonia, parkinsonism, psychomotor retardation, tongue spasm, torticollis, tremor, and trismus
** Somnolence includes adverse event terms: hypersomnia, hypersomnolence, sedation, and somnolence
Adjunctive Therapy
The following findings are based on two short-term, placebo-controlled adjunctive therapy studies for bipolar depression in which lurasidone hydrochloride tablets were administered at daily doses ranging from 20 to 120 mg as adjunctive therapy with lithium or valproate (n=360).
Commonly Observed Treatment-emergent Adverse Events: The most common adverse events (incidence >5% and at least twice the rate of placebo) in subjects treated with lurasidone hydrochloride tablets were akathisia and somnolence.
Treatment-emergent Adverse Events Associated with Discontinuation of Treatment: A total of 5.8% (21/360) of lurasidone hydrochloride tablet-treated patients and 4.8% (16/334) of placebo-treated patients discontinued due to adverse events. There were no adverse events associated with discontinuation in subjects treated with lurasidone hydrochloride tablets that were at least 2% and at least twice the placebo rate.
Treatment-emergent Adverse Events Occurring at an Incidence of 2% or More in Lurasidone Hydrochloride Tablet-treated Patients: Adverse events associated with the use of lurasidone hydrochloride tablets (incidence of 2% or greater, rounded to the nearest percent and lurasidone hydrochloride tablet incidence greater than placebo) that occurred during acute therapy (up to 6 weeks in patients with bipolar depression) are shown in Table 4.
Table 4: Treatment-emergent Adverse Events in 2% or More of Lurasidone Hydrochloride Tablet-treated Adult Patients (Adjunctive Therapy) and that Occurred at Greater Incidence than in the Placebo-treated Patients in a Short-term Bipolar Depression Study
| Percentage of Patients Reporting Reaction | ||||||
Body System or Organ Class Dictionary-derived Term | Placebo (N=334) | Lurasidone Hydrochloride Tablets (N=360) | ||||
| Gastrointestinal Disorders | ||||||
| Nausea | 10 | 14 | ||||
| Vomiting | 1 | 4 | ||||
| General Disorders | ||||||
| Fatigue | 1 | 3 | ||||
| Infections and Infestations | ||||||
| Nasopharyngitis | 2 | 4 | ||||
| Investigations | ||||||
| Weight increased | 1 | 3 | ||||
| Metabolism and Nutrition Disorders | ||||||
| Increased Appetite | 1 | 3 | ||||
| Nervous System Disorders | ||||||
| Extrapyramidal disorder** | 9 | 14 | ||||
| Somnolence* | 5 | 11 | ||||
| Akathisia | 5 | 11 | ||||
| Psychiatric Disorders | ||||||
| Restlessness | 1 | 4 | ||||
Note: Figures rounded to the nearest integer * Somnolence includes adverse event terms: hypersomnia, hypersomnolence, sedation, and somnolence ** Extrapyramidal symptoms includes adverse event terms: bradykinesia, cogwheel rigidity, drooling, dystonia, extrapyramidal disorder, hypokinesia, muscle rigidity, oculogyric crisis, oromandibular dystonia, parkinsonism, psychomotor retardation, tongue spasm, torticollis, tremor, and trismus |
Treatment-emergent Adverse Events by Concomitant Use of Lithium or Valproate: A higher incidence of treatment-emergent adverse-events was reported for lurasidone hydrochloride tablets administered with lithium compared with lurasidone hydrochloride tablets administered with valproate. Treatment-emergent adverse events associated with use of lurasidone hydrochloride tablets and lithium-treated subjects with an incidence ≥ 5% and at least twice the rate of lurasidone hydrochloride tablets and valproate-treated subjects were parkinsonism (19% versus 8%).
Children and Adolescents
Taro-Lurasidone is not indicated for the treatment of depressive episodes in bipolar I disorder in patients less than 13 years of age due to insufficient safety and efficacy data. The following findings are based on the children and adolescents short-term (6 weeks), placebo-controlled study for bipolar depression in which lurasidone hydrochloride tablets were administered at daily doses ranging from 20 to 80 mg (N=175).
Commonly Observed Adverse Reactions: The most common adverse reactions (incidence ≥5%, and at least twice the rate of placebo) in children and adolescents (10 to 17 years) treated with lurasidone hydrochloride tablets were nausea, weight increase, and insomnia.
Adverse Reactions Associated with Discontinuation of Treatment: The incidence of discontinuation due to adverse reactions between lurasidone hydrochloride tablet- and placebo-treated children and adolescents (10 to 17 years) was 2% and 2%, respectively. Fatigue, restless leg syndrome and bipolar disorder were reported in the lurasidone hydrochloride tablet-treated group. Depression, mania and psychotic disorder were reported in the placebo-treated group.
Adverse Reactions Occurring at an Incidence of 2% or More in Lurasidone Hydrochloride Tablet-Treated Patients: Adverse reactions associated with the use of lurasidone hydrochloride tablets (incidence of 2% or greater, rounded to the nearest percent and lurasidone hydrochloride tablet incidence greater than placebo) that occurred during acute therapy (up to 6 weeks in patients with bipolar depression) are shown in Table 5.
Table 5: Adverse Reactions in 2% or More of Lurasidone Hydrochloride Tablet-Treated Patients and That Occurred at Greater Incidence than in the Placebo-Treated Patients in the Children and Adolescents Short-term Bipolar Depression Study
Body System or Organ Class Dictionary-derived Term | Percentage of Patients Reporting Reaction | |
Placebo (N=172) | Lurasidone Hydrochloride Tablet 20 to 80 mg/day (N=175) | |
| Gastrointestinal Disorders | ||
| Nausea | 6 | 16 |
| Vomiting | 4 | 6 |
| Abdominal Pain Upper | 2 | 3 |
| Diarrhea | 2 | 3 |
| Abdominal Pain | 1 | 3 |
| General Disorders and Administration Site Conditions | ||
| Fatigue | 2 | 3 |
| Investigations | ||
| Weight Increased | 2 | 7 |
| Metabolism and Nutrition Disorders | ||
| Decreased Appetite | 2 | 4 |
| Nervous System Disorders | ||
| Somnolence* | 6 | 11 |
| Extrapyramidal Disorder** | 5 | 6 |
| Dizziness | 5 | 6 |
| Psychiatric Disorders | ||
| Insomnia | 2 | 5 |
| Abnormal Dreams | 2 | 2 |
| Respiratory, Thoracic and Mediastinal Disorders | ||
| Oropharyngeal Pain | 2 | 2 |
Note: Figures rounded to the nearest integer *Somnolence includes adverse event terms: hypersomnia, hypersomnolence, sedation, and somnolence **EPS includes adverse event terms: akathisia, cogwheel rigidity, dyskinesia, dystonia, hyperkinesia, joint stiffness, muscle rigidity, muscle spasms, musculoskeletal stiffness, oculogyric crisis, parkinsonism, tardive dyskinesia, and tremor |
Dose-Related Adverse Events
Schizophrenia
Adults
In pooled data from the short-term, placebo-controlled, fixed-dose studies, there were no dose-related adverse events (greater than 5% incidence) in patients treated with lurasidone hydrochloride tablets across the 20 mg/day to 160 mg/day dose range. However, the frequency of akathisia increased with dose up to 120 mg/day (5.6% lurasidone hydrochloride tablets 20 mg, 10.7% lurasidone hydrochloride tablets 40 mg, 12.3% lurasidone hydrochloride tablets 80 mg, and 22.0% lurasidone hydrochloride tablets 120 mg); akathisia was reported by 7.4% (9/121) of patients receiving 160 mg/day. Akathisia occurred in 3.0% of subjects receiving placebo.
Adolescents
In the short-term, placebo-controlled adolescent study for schizophrenia, treatment emergent adverse events reported at an incidence of ≥ 5% in either lurasidone hydrochloride tablet group (or both) and that were more common in the 80 mg/day group than the 40 mg/day group were: nausea (14.4% vs 12.7%); somnolence (11.5% vs 9.1); headache (10.6% vs 6.4%); insomnia (6.7% vs 5.5%); agitation (5.8% vs 4.5%).
Bipolar Depression
Monotherapy
In the short-term, placebo-controlled monotherapy study (involving lower and higher lurasidone hydrochloride tablet dose ranges), the adverse events that occurred with a greater than 5% incidence in the patients treated with lurasidone hydrochloride tablets in any dose group and greater than placebo in both groups were nausea (10.4%, 17.4%), somnolence (7.3%, 13.8%), akathisia (7.9%, 10.8%), parkinsonism (4.9%, 7.8%), and insomnia (4.9%, 6.6%) for lurasidone hydrochloride tablets 20-60 mg/day and lurasidone hydrochloride tablets 80-120 mg/day flexible-dose groups, respectively.
Extrapyramidal Symptoms
Schizophrenia
Adults
In the short-term, placebo-controlled schizophrenia studies in adults, for lurasidone hydrochloride tablet-treated patients, the incidence of reported EPS-related events, excluding akathisia and restlessness, was 13.5% versus 5.8% for placebo-treated patients. The incidence of akathisia for lurasidone hydrochloride tablet-treated patients was 12.9% versus 3.0% for placebo-treated patients. The frequency of EPS events in general increased with dose up to 120 mg/day. Incidence of EPS in adults by dose is provided in Table 6.
Table 6: Percentage of EPS Compared to Placebo in Short-term Schizophrenia Studies in Adults
| Adverse Event Term | Placebo (N=708) (% ) | Lurasidone Hydro-chloride Tablets 20 mg/day (N=71) (% ) | Lurasidone Hydro-chloride Tablets 40 mg/day (N=487) (% ) | Lurasidone Hydro-chloride Tablets 80 mg/day (N=538) (% ) | Lurasidone Hydro-chloride Tablets 120 mg/day (N=291) (% ) | Lurasidone Hydro-chloride Tablets 160 mg/day (N=121) (% ) |
| All EPS events | 9 | 10 | 21 | 23 | 39 | 20 |
| All EPS events, excluding Akathisia/Restlessness | 6 | 6 | 11 | 12 | 22 | 13 |
| Akathisia | 3 | 6 | 11 | 12 | 22 | 7 |
| Dystonia* | <1 | 0 | 4 | 5 | 7 | 2 |
| Parkinsonism** | 5 | 6 | 9 | 8 | 17 | 11 |
| Restlessness | 1 | 1 | 3 | 1 | 3 | 2 |
Note: Figures rounded to the nearest integer * Dystonia includes adverse event terms: dystonia, oculogyric crisis, oromandibular dystonia, tongue spasm, torticollis, and trismus |
| ** Parkinsonism includes adverse event terms: bradykinesia, cogwheel rigidity, drooling, extrapyramidal disorder, hypokinesia, muscle rigidity, parkinsonism, psychomotor retardation, and tremor |
Adolescents
In the short-term, placebo-controlled schizophrenia study in adolescent patients (13 to 17 years), the incidence of extrapyramidal symptoms (EPS), excluding events related to akathisia, for lurasidone hydrochloride tablet-treated patients was higher in the 40 mg (10%) and the 80 mg (7.7%) treatment groups vs. placebo (3.6%); and the incidence of akathisia-related events for lurasidone hydrochloride tablet-treated patients was 8.9% vs. 1.8% for placebo-treated patients. Incidence of EPS in adolescents by dose is provided in Table 7.
Table 7: Incidence of EPS Compared to Placebo in Adolescent Schizophrenia Study
| Lurasidone Hydrochloride Tablets | |||||||
| Adverse Event Term | Placebo (N=112) (% ) | 40 mg/day (N=110) (% ) | 80 mg/day (N=104) (% ) | ||||
| All EPS events | 5 | 14 | 14 | ||||
| All EPS events, excluding Akathisia/Restlessness | 4 | 10 | 8 | ||||
| Akathisia | 2 | 9 | 9 | ||||
| Parkinsonism** | <1 | 4 | 0 | ||||
| Dyskinesia | <1 | <1 | 1 | ||||
| Dystonia* | 0 | <1 | 1 | ||||
Note: Figures rounded to the nearest integer * Dystonia includes adverse event terms: dystonia, trismus, oculogyric crisis, oromandibular dystonia, tongue spasm, and torticollis ** Parkinsonism includes adverse event terms: bradykinesia, drooling, extrapyramidal disorder, glabellar reflex abnormal, hypokinesia, parkinsonism, and psychomotor retardation |
Bipolar Depression
Adults
Monotherapy
In the short-term, placebo-controlled monotherapy study, for lurasidone hydrochloride tablet-treated patients, the incidence of reported events related to EPS, excluding akathisia and restlessness, was 6.9% versus 2.4% for placebo-treated patients. The incidence of akathisia for lurasidone hydrochloride tablet-treated patients was 9.4% versus 2.4% for placebo-treated patients. Incidence of EPS by dose groups is provided in Table 8.
Table 8: Percentage of EPS Compared to Placebo in the Monotherapy Bipolar Depression Study in Adults
| Lurasidone Hydrochloride Tablet | ||||||||
| Adverse Event Term | Placebo (N=168) (% ) | 20 to 60 mg/day (N=164) (% ) | 80 to 120 mg/day (N=167) (% ) | |||||
| All EPS events | 5 | 12 | 20 | |||||
| All EPS events, excluding Akathisia/Restlessness | 2 | 5 | 9 | |||||
| Akathisia | 2 | 8 | 11 | |||||
| Dystonia* | 0 | 0 | 2 | |||||
| Parkinsonism** | 2 | 5 | 8 | |||||
| Restlessness | <1 | 0 | 3 | |||||
Note: Figures rounded to the nearest integer * Dystonia includes adverse event terms: dystonia, oculogyric crisis, oromandibular dystonia, tongue spasm, torticollis, and trismus ** Parkinsonism includes adverse event terms: bradykinesia, cogwheel rigidity, drooling, extrapyramidal disorder, glabellar reflex abnormal, hypokinesia, muscle rigidity, parkinsonism, psychomotor retardation, and tremor |
Adjunctive Therapy
In the short-term, flexible-dose, placebo-controlled adjunctive therapy studies, for lurasidone hydrochloride tablet-treated patients, the incidence of reported events related to EPS, excluding akathisia and restlessness, was 13.9% versus 8.7% for placebo-treated patients. The incidence of akathisia for lurasidone hydrochloride tablet-treated patients was 10.8 % versus 4.8% for placebo-treated patients. Incidence of EPS is provided in Table 9.
Table 9: Percentage of EPS Compared to Placebo in the Adjunctive Therapy Bipolar Depression Studies in Adults
| Adverse Event Term | Placebo (N=334) (% ) | ALL Lurasidone Hydrochloride Tablet 20 to 60 mg/day (N=360) (% ) |
| All EPS events | 13 | 24 |
| All EPS events, excluding Akathisia/Restlessness | 9 | 14 |
| Akathisia | 5 | 11 |
| Dystonia* | 1 | 1 |
| Parkinsonism** | 8 | 13 |
| Restlessness | 1 | 4 |
Note: Figures rounded to the nearest integer * Dystonia includes adverse event terms: dystonia, oculogyric crisis, oromandibular dystonia, tongue spasm, torticollis, and trismus ** Parkinsonism includes adverse event terms: bradykinesia, cogwheel rigidity, drooling, extrapyramidal disorder, glabellar reflex abnormal, hypokinesia, muscle rigidity, parkinsonism, psychomotor retardation, and tremor |
Children and Adolescents
In the children and adolescents short-term, placebo-controlled study of bipolar depression, the incidence of EPS, excluding events related to akathisia, was similar in the lurasidone hydrochloride tablets 20 to 80 mg/day (3.4%) treatment group to placebo (3.5%); and the incidence of akathisia-related events for lurasidone hydrochloride tablet-treated patients was 2.9% vs. 3.5% for placebo-treated patients. Incidence of EPS is provided in Table 10.
Table 10: Incidence of EPS Compared to Placebo in the Children and Adolescents Bipolar Depression Study
| Adverse Event Term | Placebo (N=172) (% ) | Lurasidone Hydrochloride Tablets 20 to 80 mg/day (N=175) (% ) |
| All EPS events* | 5 | 6 |
| All EPS events, excluding Akathisia/Restlessness | 4 | 3 |
| Akathisia | 4 | 3 |
| Parkinsonism** | <1 | <1 |
| Dystonia*** | 1 | <1 |
| Salivary hypersecretion | <1 | <1 |
| Psychomotor hyperactivity | 0 | <1 |
| Tardive Dyskinesia | <1 | 0 |
Note: Figures rounded to the nearest integer * EPS includes adverse event terms: akathisia, cogwheel rigidity, dyskinesia, dystonia, hyperkinesia, joint stiffness, muscle rigidity, muscle spasms, musculoskeletal stiffness, oculogyric crisis, parkinsonism, tardive dyskinesia, and tremor ** Parkinsonism includes adverse event terms: bradykinesia, drooling, extrapyramidal disorder, glabellar reflex abnormal, hypokinesia, parkinsonism, and psychomotor retardation ***Dystonia includes adverse event terms: dystonia, oculogyric crisis, oromandibular dystonia, tongue spasm, torticollis, and trismus |
In the short-term, placebo-controlled schizophrenia and bipolar depression studies, data was objectively collected on the Simpson Angus Rating Scale (SAS) for extrapyramidal symptoms (EPS), the Barnes Akathisia Scale [BAS (for akathisia)], and the Abnormal Involuntary Movement Scale [AIMS (for dyskinesias)].
Schizophrenia
Adults
The mean change from baseline to last assessment for lurasidone hydrochloride tablet-treated adult patients was comparable to placebo-treated patients, with the exception of the BAS total score (lurasidone hydrochloride tablets, 0.2; placebo, 0.0) and global clinical assessment score (lurasidone hydrochloride tablets, 0.1; placebo, 0.0). The percentage of patients who shifted from normal/questionable at baseline to abnormal at any post-baseline assessment was greater in lurasidone hydrochloride tablet-treated patients versus placebo for the BAS global clinical assessment (lurasidone hydrochloride tablets, 18.0%; placebo, 7.8%) and the SAS score (lurasidone hydrochloride tablets, 14.9%; placebo, 6.2%).
Adolescents
The mean change from baseline for lurasidone hydrochloride tablet-treated patients with adolescent schizophrenia for the SAS, BAS and AIMS was comparable to placebo-treated patients. The percentage of patients who shifted from normal to abnormal was greater in lurasidone hydrochloride tablet-treated patients versus placebo for the BAS (lurasidone hydrochloride tablets, 7.0%; placebo, 1.8%), the SAS (lurasidone hydrochloride tablets, 8.3%; placebo, 2.7%) and the AIMS (lurasidone hydrochloride tablets, 2.8%; placebo, 0.9%).
Bipolar Depression
Adults
Monotherapy
The mean change from baseline for lurasidone hydrochloride tablet-treated patients for the SAS, BAS and AIMS was comparable to placebo-treated patients. The percentage of patients who shifted from normal/questionable at baseline to abnormal at any post-baseline assessment was greater in lurasidone hydrochloride tablet-treated patients versus placebo for the BAS global clinical assessment (lurasidone hydrochloride tablets, 12.1%; placebo, 3.7%) and the SAS score (lurasidone hydrochloride tablets, 8.4%; placebo, 4.3%).
Adjunctive Therapy
The mean change from baseline for lurasidone hydrochloride tablet-treated patients for the SAS, BAS and AIMS was comparable to placebo-treated patients. The percentage of patients who shifted from normal/questionable at baseline to abnormal at any post-baseline assessment was greater in lurasidone hydrochloride tablet-treated patients versus placebo for the BAS global clinical assessment (lurasidone hydrochloride tablets, 12.2%; placebo, 3.2%) and the SAS score (lurasidone hydrochloride tablets, 8.2%; placebo, 6.1%) and the AIMS (lurasidone hydrochloride tablets 1.7%, placebo 0.6%).
Children and Adolescents
The mean change from baseline for lurasidone hydrochloride tablet-treated children and adolescents with bipolar depression for the SAS, BAS and AIMS was comparable to placebo-treated patients. The percentage of patients who shifted from normal to abnormal was greater in lurasidone hydrochloride tablet-treated patients versus placebo for the BAS (lurasidone hydrochloride tablets, 4.6%; placebo, 2.4 %), the SAS (lurasidone hydrochloride tablets, 0.6%; placebo, 0%) and was the same for the AIMS (lurasidone hydrochloride tablets, 0%; placebo, 0%).
Dystonia
Symptoms of dystonia, prolonged abnormal contractions of muscle groups, may occur in susceptible individuals during the first few days of treatment. Dystonic symptoms include: spasm of the neck muscles, sometimes progressing to tightness of the throat, swallowing difficulty, difficulty breathing, and/or protrusion of the tongue. While these symptoms can occur at low doses, they occur more frequently and with greater severity with high potency and at higher doses of first generation antipsychotic drugs. An elevated risk of acute dystonia is observed in males and younger age groups.
Schizophrenia
Adults
In the short-term, placebo-controlled clinical trials, dystonia occurred in 4.2% of lurasidone hydrochloride tablet-treated subjects (0.0% lurasidone hydrochloride tablets 20 mg, 3.5% lurasidone hydrochloride tablets 40 mg, 4.5% lurasidone hydrochloride tablets 80 mg, 6.5% lurasidone hydrochloride tablets 120 mg, and 2.5% lurasidone hydrochloride tablets 160 mg) compared to 0.8% of subjects receiving placebo. Seven subjects (0.5%, 7/1508) discontinued clinical trials due to dystonic events – four were receiving lurasidone hydrochloride tablets 80 mg/day and three were receiving lurasidone hydrochloride tablets 120 mg/day.
Adolescents
In the short-term, placebo-controlled study of schizophrenia in adolescent patients (13 to 17 years), dystonia occurred in 1% of lurasidone hydrochloride tablet-treated subjects (1% lurasidone hydrochloride tablets 40 mg and 1% lurasidone hydrochloride tablets 80 mg) compared to 0% of subjects receiving placebo. No subject discontinued clinical study due to dystonic events.
Bipolar Depression
Adults
Monotherapy
In the short-term, placebo-controlled monotherapy study, dystonia occurred in 0.9% of lurasidone hydrochloride tablet-treated subjects (0.0% and 1.8% for lurasidone hydrochloride tablets 20-60 mg/day and lurasidone hydrochloride tablets 80-120 mg/day flexible-dose groups, respectively) compared to 0.0% of subjects receiving placebo. No subject discontinued the clinical study due to dystonic events.
Adjunctive Therapy
In the short-term, flexible-dose, placebo-controlled adjunctive therapy studies, dystonia occurred in 1.1% of lurasidone hydrochloride tablet-treated subjects (20-120 mg) compared to 0.6% of subjects receiving placebo. No subject discontinued the clinical study due to dystonic events.
Children and Adolescents
In the children and adolescents short-term, placebo-controlled bipolar depression study, dystonia occurred in 0.6% of lurasidone hydrochloride tablet-treated patients compared to 1.2% of patients receiving placebo. No patients discontinued the clinical study due to dystonic events.
Weight Gain
Schizophrenia
Adults
Pooled data from short-term, placebo-controlled schizophrenia studies are presented in Table 11. The mean weight change was a 0.43 kg increase for lurasidone hydrochloride tablet-treated patients compared to a 0.02 kg decrease for placebo-treated patients. In two 6-week studies that included active comparators, the mean weight gain at the last assessment in the study was 0.98 kg for lurasidone hydrochloride tablets 40 mg, 1.05 kg for lurasidone hydrochloride tablets 120 mg, and 4.15 kg for olanzapine 15 mg in one study, and 0.62 kg for lurasidone hydrochloride tablets 80 mg, 0.60 kg for lurasidone hydrochloride tablets 160 mg, and 2.09 kg for quetiapine XR 600 mg in another study. The proportion of patients with a ≥7% increase in body weight (at Endpoint) was 4.8% for lurasidone hydrochloride tablet-treated patients versus 3.3% for placebo-treated patients
Table 11: Mean Change in Weight (kg) from Baseline to Last Assessment in Short-term Schizophrenia Studies in Adults
Placebo (n=696) | Lurasidone Hydro-chloride Tablets 20 mg/day (n=71) | Lurasidone Hydro-chloride Tablets 40 mg/day (n=484) | Lurasidone Hydro-chloride Tablets 80 mg/day (n=526) | Lurasidone Hydro-chloride Tablets 120 mg/day (n=291) | Lurasidone Hydro-chloride Tablets 160 mg/day (n=114) | |
| All Patients | -0.02 | -0.15 | 0.22 | 0.54 | 0.68 | 0.60 |
Adolescents
Data from the short-term, placebo-controlled adolescent schizophrenia study are presented in Table 12. The mean weight gain was 0.5 kg for lurasidone hydrochloride tablet-treated patients (0.3 kg for 40 mg and 0.7 kg for 80 mg dose) compared to 0.2 kg for placebo-treated patients. The proportion of patients with a ≥ 7% increase in body weight (at Endpoint) was 2.3% for lurasidone hydrochloride tablet-treated patients (2.8% for 40 mg and 1.9% for 80 mg dose) versus 4.5% for placebo-treated patients. Weight gain as an adverse event was reported in 3 (2.9%) subjects receiving lurasidone hydrochloride tablets 80 mg/day, 1 (0.9%) subject receiving lurasidone hydrochloride tablets 40 mg/day, and 3 (2.7%) subjects receiving placebo.
Table 12: Mean Change in Weight (kg) from Baseline in Adolescent Schizophrenia Study
| Lurasidone Hydrochloride Tablets | |||||||
Placebo (n=111) | 40 mg/day (n=109) | 80 mg/day (n=104) | |||||
| All Patients | +0.2 | +0.3 | +0.7 | ||||
Bipolar Depression
Adults
Monotherapy
Data from the short-term, placebo-controlled monotherapy study are presented in Table 13. The mean weight gain was 0.29 kg for lurasidone hydrochloride tablet-treated patients compared to -0.04 kg for placebo-treated patients. The proportion of patients with a ≥ 7% increase in body weight (at Endpoint) was 2.4% for lurasidone hydrochloride tablet-treated patients versus 0.7% for placebo-treated patients.
Table 13: Mean Change in Weight (kg) from Baseline in the Monotherapy Bipolar Depression Study in Adults
| Lurasidone Hydrochloride Tablets | |||||||
Placebo (n=151) | 20 to 60 mg/day (n=143) | 80 to 120 mg/day (n=147) | |||||
| All Patients | -0.04 | 0.56 | 0.02 | ||||
Patients were randomized to flexibly dosed lurasidone hydrochloride tablets 20-60 mg/day, lurasidone hydrochloride tablets 80-120 mg/day or placebo
Adjunctive Therapy
Data from the short-term, flexible-dose, placebo-controlled adjunctive therapy studies are presented in Table 14. The mean weight gain was 0.11 kg for lurasidone hydrochloride tablet-treated patients compared to 0.16 kg for placebo-treated patients. The proportion of patients with a ≥ 7% increase in body weight (at Endpoint) was 3.1% for lurasidone hydrochloride tablet-treated patients versus 0.3% for placebo-treated patients.
Table 14: Mean Change in Weight (kg) from Baseline in the Adjunctive Therapy Bipolar Depression Studies in Adults
Placebo (n=334) | Lurasidone Hydrochloride Tablets 20 to 120 mg/day (n=360) | |
| All Patients | 0.16 | 0.11 |
Patients were randomized to flexibly dosed lurasidone hydrochloride tablets 20-120 mg/day or placebo as adjunctive therapy with lithium or valproate
Children and Adolescents
Data from the children and adolescents short-term, placebo-controlled bipolar depression study are presented in Table 15. Seven percent (7%) of lurasidone hydrochloride tablet-treated patients reported weight gain as an adverse event compared to 2% of placebo-treated patients. The mean weight gain was 0.7 kg for lurasidone hydrochloride tablet-treated patients compared to 0.5 kg for placebo-treated patients. The proportion of patients with a ≥7% increase in body weight (at Endpoint) was 4.0% for lurasidone hydrochloride tablet-treated patients versus 5.3% for placebo-treated patients.
Table 15: Mean Change in Weight (kg) from Baseline in the Children and Adolescents Bipolar Depression Study
Placebo (n=170) | Lurasidone Hydrochloride Tablets 20 to 80 mg/day (n=175) | |
| All Patients | +0.5 | +0.7 |
Constipation
Patients should be advised of the risk of severe constipation during lurasidone hydrochloride tablet treatment, and they should tell their doctor if constipation occurs or worsens, since they may need laxatives.
Less Common Clinical Trial Adverse Drug Reactions (<2%)
Following is a list of MedDRA terms that reflect adverse events reported by patients treated with lurasidone hydrochloride tablets at multiple doses of ≥20 mg once daily during any phase of a study within the database of 2905 adult patients. The events listed are those that could be of clinical importance, as well as events that are plausibly drug-related on pharmacologic or other grounds.
Events listed in Table 1 are not included. Although the events reported occurred during treatment with lurasidone hydrochloride tablets, they were not necessarily caused by it.
Events are further categorized by MedDRA system organ class and listed in order of decreasing frequency according to the following definitions: those occurring in at least 1/100 patients (frequent) (only those not already listed in the tabulated results from placebo-controlled studies appear in this listing); those occurring in 1/100 to 1/1000 patients (infrequent); and those occurring in fewer than 1/1000 patients (rare).
Blood and Lymphatic System Disorders:
Infrequent: anemia;
Rare: leukopenia, neutropenia
Cardiac Disorders:
Frequent: tachycardia;
Infrequent: AV block 1st degree, angina pectoris, bradycardia, ventricular extrasystoles, arrhythmia
Ear and Labyrinth Disorders:
Infrequent: tinnitus, vertigo
Eye Disorders:
Frequent: blurred vision;
Infrequent: visual impairment
Gastrointestinal Disorders:
Frequent: abdominal pain, constipation, diarrhea, dry mouth;
Infrequent: gastritis, gastroesophageal reflux disease, dysphagia, tongue disorder;
Rare: swollen tongue
General Disorders and Administrative Site Conditions:
Frequent: fatigue, pyrexia;
Infrequent: asthenia, gait disturbance, irritability, peripheral edema, sudden death
Hepatobiliary Disorders:
Infrequent: hepatic function abnormal, hepatic steatosis, jaundice
Immune System Disorders:
Rare: drug hypersensitivity
Investigations:
Frequent: blood prolactin increased, blood triglycerides increased, CPK increased, weight increased, weight decreased;
Infrequent: blood pressure decreased, blood uric acid increased, body temperature increased, white blood cell count increased;
Rare: electrocardiogram T wave inversion
Metabolism and Nutritional System Disorders:
Frequent: decreased appetite;
Infrequent: anorexia, dehydration, diabetes mellitus, increased appetite
Musculoskeletal and Connective Tissue Disorders:
Frequent: musculoskeletal stiffness, myalgia;
Rare: rhabdomyolysis
Nervous System Disorders:
Frequent: dyskinesia;
Infrequent: tardive dyskinesia, cerebrovascular accident, convulsion, dysarthria, dysgeusia, hypoaesthesia, paresthesia, syncope;
Rare: neuroleptic malignant syndrome, seizure
Psychiatric Disorders:
Frequent: depression;
Infrequent: abnormal dreams, apathy, confusional state, hostility, panic attack, sleep disorder, suicidal ideation, completed suicide, suicide attempt;
Rare: somnambulism, suicidal behavior
Renal and Urinary Disorders:
Infrequent: dysuria, urinary incontinence;
Rare: renal failure
Reproductive System and Breast Disorders:
Infrequent: amenorrhea, dysmenorrhea, menstruation irregular, erectile dysfunction;
Rare: breast enlargement, breast pain, galactorrhea
Respiratory disorders:
Infrequent: dyspnea;
Rare: pneumonia aspiration
Skin and Subcutaneous Tissue Disorders:
Frequent: rash (including erythematous, exfoliative, generalized, maculopapular, papular rash, pruritic; atopic, allergic, contact, seborrheic dermatitis, neurodermatitis), pruritus;
Infrequent: hyperhidrosis, urticaria;
Rare: angioedema
Vascular Disorders:
Frequent: hypertension;
Infrequent: hot flush, hypotension, orthostatic hypotension;
Rare: thrombophlebitis superficial
Pediatric and adolescent patients (10-17 years of age) with bipolar depression
Most adverse reactions observed in the pediatric and adolescent patients with bipolar depression aged 10 - 17 years were also observed in the adult population. Additional adverse reactions observed in the pediatric and adolescent population are listed below.
Investigations:
Frequent: C-Reactive Protein Increased
Abnormal Hematologic and Clinical Chemistry Findings
Laboratory Test Abnormalities
In a between-group comparison of the pooled data from short-term, placebo-controlled studies, there were no clinically important changes in total cholesterol measurements, triglycerides, or glucose from Baseline to Endpoint [see WARNINGS AND PRECAUTIONS]. There were also no clinically important differences between lurasidone hydrochloride tablets and placebo in mean change from baseline to endpoint in routine hematology, urinalysis, or serum chemistry. Lurasidone hydrochloride tablets were associated with a dose-related increase in prolactin concentration [see WARNINGS AND PRECAUTIONS].
Glucose:
Schizophrenia
Adults
Pooled data from short-term, placebo-controlled schizophrenia studies are presented in Table 16.
Table 16: Change in Fasting Glucose in Schizophrenia Studies from Baseline to Last Study Assessment in Pooled Short-term Studies in Adults
| Placebo | Lurasidone Hydro-chloride Tablets 20 mg/day | Lurasidone Hydro-chloride Tablets 40 mg/day | Lurasidone Hydro-chloride Tablets 80 mg/day | Lurasidone Hydro-chloride Tablets 120 mg/day | Lurasidone Hydro-chloride Tablets 160 mg/day | |||||||||||
| Mean Change from Baseline (mmol/L) | ||||||||||||||||
| n=601 | n=70 | n=417 | n=481 | n=220 | n=97 | |||||||||||
| Serum Glucose | 0.03 | -0.11 | 0.13 | -0.01 | 0.12 | 0.21 | ||||||||||
| Proportion of Patients with Shifts to ≥7 mmol/L | ||||||||||||||||
Serum Glucose ( ≥7 mmol/L) | 5.8% (33/565) | 8.2% (5/61) | 9.6% (38/395) | 5.3% (24/452) | 4.8% (10/209) | 5.3% (5/95) | ||||||||||
Adolescents
Data from the short-term (6 week), placebo-controlled schizophrenia study are presented in Table 17.
Table 17: Change in Fasting Glucose in Adolescent Schizophrenia Study
| Lurasidone Hydrochloride Tablets | |||||||||
| Placebo | 40 mg/day | 80 mg/day | |||||||
| Mean Change from Baseline (mmol/L) | |||||||||
| n=95 | n=90 | n=92 | |||||||
| Serum Glucose | -0.07 | +0.01 | +0.10 | ||||||
| Proportion of Patients with Shifts to ≥ 7 mmol/L | |||||||||
Serum Glucose ≥ 7 mmol/L) | 0% (0/95) | 0% (0/90) | 1% (1/92) | ||||||
Bipolar Depression
Adults
Monotherapy
Data from the short-term, placebo-controlled monotherapy study are presented in Table 18.
Table 18: Change in Fasting Glucose in the Monotherapy Bipolar Depression Study in Adults
| Lurasidone Hydrochloride Tablets | |||||||||||
| Placebo | 20 to 60 mg/day | 80 to 120 mg/day | |||||||||
| Mean Change from Baseline (mmol/L) | |||||||||||
| n=148 | n=140 | n=143 | |||||||||
| Serum Glucose | -0.10 | -0.04 | 0.10 | ||||||||
| Proportion of Patients with Shifts to ≥ 7 mmol/L | |||||||||||
Serum Glucose (≥ 7 mmol/L) | 4.3% (6/141) | 2.2% (3/138) | 6.4% (9/141) | ||||||||
Patients were randomized to flexibly dosed lurasidone hydrochloride tablets 20-60 mg/day, lurasidone hydrochloride tablets 80-120 mg/day or placebo
Adjunctive Therapy
Data from the short-term, flexible-dose, placebo-controlled adjunctive therapy studies are presented in Table 19.
Table 19: Change in Fasting Glucose in the Adjunctive Therapy Bipolar Depression Studies in Adults
| Placebo | Lurasidone Hydrochloride Tablets 20 to 120 mg/day | ||||||
| Mean Change from Baseline (mmol/L) | |||||||
| n=302 | n=319 | ||||||
| Serum Glucose | 0.05 | 0.07 | |||||
| Proportion of Patients with Shifts to ≥ 7 mmol/L | |||||||
Serum Glucose (≥ 7 mmol/L) | 1.0% (3/290) | 1.3% (4/316) | |||||
Patients were randomized to flexibly dosed lurasidone hydrochloride tablets 20-120 mg/day or placebo as adjunctive therapy with lithium or valproate.
Children and Adolescents
Data from the short-term, placebo-controlled bipolar depression study are presented in Table 20.
Table 20: Change in Fasting Glucose in the Children and Adolescents Bipolar Depression Study
| Placebo | 20 to 80 mg/day | ||||||
| Mean Change from Baseline at Endpoint (mmol/L) | |||||||
| n=145 | n=145 | ||||||
| Serum Glucose | -0.03 | 0.08 | |||||
| Proportion of Patients with Shifts to ≥ 7 mmol/L During the Post-Baseline Treatment Period | |||||||
Serum Glucose (≥ 7 mmol/L) | 0% (0/148) | 1.3% (2/150) | |||||
Cholesterol and Triglycerides:
Schizophrenia
Adults
Pooled data from short-term, placebo-controlled schizophrenia studies with lurasidone are presented in Table 21.
Table 21: Change in Fasting Lipids in Schizophrenia Studies from Baseline to Last Study Assessment in Pooled Short-term Studies in Adults
| Placebo | Lurasidone Hydro-chloride Tablets 20 mg/day | Lurasidone Hydro-chloride Tablets 40 mg/day | Lurasidone Hydro-chloride Tablets 80 mg/day | Lurasidone Hydro-chloride Tablets 120 mg/day | Lurasidone Hydro-chloride Tablets 160 mg/day | |||||||||||
| Mean Change from Baseline (mmol/L) | ||||||||||||||||
| n=567 | n=70 | n=387 | n=465 | n=182 | n=100 | |||||||||||
| Total cholesterol | -0.15 | -0.29 | -0.12 | -0.15 | -0.13 | -0.19 | ||||||||||
| Triglycerides | -0.17 | -0.36 | -0.11 | -0.18 | -0.06 | -0.17 | ||||||||||
| Proportion of Patients with Shifts | ||||||||||||||||
Total cholesterol ( ≥6.2 mmol/L) | 5.2% (26/497) | 12.1% (7/58) | 5.6% (19/339) | 5.2% (21/405) | 2.5% (4/161) | 4.5% (4/88) | ||||||||||
Triglycerides ( ≥2.3 mmol/L) | 7.7% (36/467) | 10.0% (5/50) | 7.4% (24/323) | 5.9% (22/371) | 6.5% (10/154) | 4.7% (4/85) | ||||||||||
Adolescents
Data from short-term (6 week), placebo-controlled schizophrenia study for adolescent (13 to 17 years) patients are presented in Table 22.
Table 22: Change in Fasting Lipids in Adolescent Schizophrenia Study
| Lurasidone Hydrochloride Tablets | ||||||||
| Placebo | 40 mg/day | 80 mg/day | ||||||
| Mean Change from Baseline (mmol/L) | ||||||||
| n=95 | n=89 | n=92 | ||||||
| Total cholesterol | -0.25 | -0.11 | +0.04 | |||||
| Triglycerides | +0.00 | -0.01 | +0.10 | |||||
| Proportion of Patients with Shifts | ||||||||
Total Cholesterol (≥ 6.0 mmol/L) | 0% (0/95) | 0% (0/89) | 3.3% (3/92) | |||||
Triglycerides (≥ 2.3 mmol/L) | 7.4% (7/95) | 3.4% (3/89) | 3.3% (3/92) | |||||
Bipolar Depression
Adults
Monotherapy
Data from the short-term, placebo-controlled, monotherapy study are presented in Table 23.
Table 23: Change in Fasting Lipids in the Monotherapy Bipolar Depression Study in Adults
| Lurasidone Hydrochloride Tablets | ||||||||||
| Placebo | 20 to 60 mg/day | 80 to 120 mg/day | ||||||||
| Mean Change from Baseline (mmol/L) | ||||||||||
| n=133 | n=125 | n=134 | ||||||||
| Total Cholesterol | -0.09 | 0.04 | -0.13 | |||||||
| Triglycerides | 0.02 | 0.08 | 0.02 | |||||||
| Proportion of Patients with Shifts | ||||||||||
Total Cholesterol (≥ 6.2 mmol/L) | 3.8% (4/104) | 3.9% (4/102) | 4.7% (5/107) | |||||||
Triglycerides (≥ 2.3 mmol/L) | 3.5% (4/114) | 11.1% (12/108) | 10.4% (12/115) | |||||||
Patients were randomized to flexibly dosed lurasidone hydrochloride tablets 20-60 mg/day, lurasidone hydrochloride tablets 80-120 mg/day or placebo
Adjunctive Therapy
Data from the short-term, flexible-dose, placebo-controlled, adjunctive therapy studies are presented in Table 24.
Table 24: Change in Fasting Lipids in the Adjunctive Therapy Bipolar Depression Studies in Adults
| Lurasidone Hydrochloride Tablets | |||||||
| Placebo | 20 to 120 mg/day | ||||||
| Mean Change from Baseline (mmol/L) | |||||||
| n=273 | n=290 | ||||||
| Total Cholesterol | -0.08 | -0.10 | |||||
| Triglycerides | -0.11 | 0.11 | |||||
| Proportion of Patients with Shifts | |||||||
Total Cholesterol (≥ 6.2 mmol/L) | 6.0% (14/235) | 5.6% (14/251) | |||||
Triglycerides (≥ 2.3 mmol/L) | 8.6% (19/220) | 10.8% (26/240) | |||||
Patients were randomized to flexibly dosed lurasidone hydrochloride tablets 20-120 mg/day or placebo as adjunctive therapy with lithium or valproate.
Children and Adolescents
Data from the short-term, placebo-controlled bipolar depression study for children and adolescents (10 to 17 years) are presented in Table 25.
Table 25: Change in Fasting Lipids in the Children and Adolescents Bipolar Depression Study
| Lurasidone Hydrochloride Tablets | ||||||||
| Placebo | 20 to 80 mg/day | |||||||
| Mean Change from Baseline at Endpoint (mmol/L) | ||||||||
| n=145 | n=144 | |||||||
| Total Cholesterol | -0.04 | -0.16 | ||||||
| Triglycerides | 0.07 | -0.09 | ||||||
| Proportion of Patients with Shifts During the Post-Baseline Treatment Period | ||||||||
Total cholesterol (≥ 6.2 mmol/L) | 3.4% (5/148) | 1.3% (2/149) | ||||||
Triglycerides (male: ≥ 2.3 mmol/L; female: ≥ 1.9 mmol/L ) | 5.4% (8/148) | 5.4% (8/149) | ||||||
Hyperprolactinemia:
Schizophrenia
Adults
In short-term, placebo-controlled schizophrenia studies, the median change from baseline to endpoint in prolactin levels for lurasidone hydrochloride tablet-treated patients was 0.4 ng/mL and -1.9 ng/mL in placebo-treated patients. The median change from baseline to endpoint for males was 0.5 ng/mL and for females was -0.2 ng/mL. The mean change from baseline to endpoint in prolactin levels in lurasidone hydrochloride tablet-treated patients with normal prolactin levels at baseline (n=1039) was 8.6 ng/mL compared to 0.4 ng/mL in placebo-treated patients (n=460), and was higher in female patients (18.4 ng/mL) compared to male patients (4.8 ng/mL).
The proportion of patients with prolactin elevations ≥5X ULN was 2.8% for lurasidone hydrochloride tablet-treated patients versus 1.0% for placebo-treated patients. The proportion of female patients with prolactin elevations ≥5X ULN was 5.7% for lurasidone hydrochloride tablet-treated patients versus 2.0% for placebo-treated female patients. The proportion of male patients with prolactin elevations ≥5X ULN was 1.6% versus 0.6% for placebo-treated male patients. The proportion of patients with elevations (≥5X ULN) in prolactin at any post-baseline assessment in the pooled short-term studies is shown in Table 26.
Table 26: Proportion of Patients with Elevations (≥5X ULN) in Prolactin (ng/mL) at any Post-baseline Assessment in Pooled Short-term Schizophrenia Studies in Adults
| Placebo | Lurasidone Hydrochloride Tablets 20 mg/day | Lurasidone Hydrochloride Tablets 40 mg/day | Lurasidone Hydrochloride Tablets 80 mg/day | Lurasidone Hydrochloride Tablets 120 mg/day | Lurasidone Hydrochloride Tablets 160 mg/day | |
| All Patients | 1.0% (n=673) | 2.9% (n=70) | 2.9% (n=476) | 2.2% (n=495) | 4.2% (n=284) | 0.9% (n=115) |
| Females | 2.0% (n=200) | 10.5% (n=19) | 6.0% (n=149) | 3.3% (n=150) | 10.0% (n=70) | 2.8% (n=36) |
| Males | 0.6% (n=473) | 0% (n=51) | 1.5% (n=327) | 1.7% (n=345) | 2.3% (n=214) | 0% (n=79) |
Adolescents
In a short-term (6 week), placebo-controlled adolescent schizophrenia study, the median change from baseline to endpoint in prolactin levels for lurasidone hydrochloride tablet-treated patients was +1.1 ng/mL and was +0.1 ng/mL in the placebo-treated patients. For lurasidone hydrochloride tablet-treated patients, the median change from baseline to endpoint for males was +1.0 ng/mL and for females was +2.6 ng/mL. Median changes for prolactin by dose are shown in Table 27.
The mean change (± SD) from baseline to endpoint in serum prolactin was -0.8 ng/mL, +0.9 ng/mL, and +4.0 ng/mL in the placebo, lurasidone 40 mg/day and 80 mg/day groups, respectively.
The proportion of patients with prolactin elevations ≥5X ULN was 0.5% for lurasidone hydrochloride tablet-treated patients (1.0% for 40 mg and 0% for 80 mg dose) versus 1.0% for placebo-treated patients. The proportion of female patients with prolactin elevations 5X ULN was 1.3% for lurasidone hydrochloride tablet-treated patients (2.4% for 40 mg and 0% for 80 mg dose) versus 0% for placebo-treated female patients. The proportion of male patients with prolactin elevations 5X ULN was 0% versus 1.6% for placebo-treated male patients.
Table 27: Median Change in Prolactin (ng/mL) from Baseline in Adolescent Schizophrenia Study
| Placebo | Lurasidone Hydrochloride Tablets 40 mg/ day | Lurasidone Hydrochloride Tablets 80 mg/ day | |
| All Patients | +0.10 (n=103) | +0.75 (n=102) | +1.20 (n=99) |
| Females | +0.70 (n=39) | +0.60 (n=42) | +4.40 (n=33) |
| Males | 0.00 (n=64) | +0.75 (n=60) | +1.00 (n=66) |
Bipolar Depression
Adults
Monotherapy
The median change from baseline to endpoint in prolactin levels, in the short-term, placebo-controlled monotherapy study, was 1.7 ng/mL and 3.5 ng/mL with lurasidone hydrochloride tablets 20-60 mg/day and lurasidone hydrochloride tablets 80-120 mg/day flexible-dose groups, respectively, compared to 0.3 ng/mL with placebo-treated patients. The median change from baseline to endpoint for males was 1.5 ng/mL and for females was 3.1 ng/mL, the mean change from baseline to endpoint in prolactin levels in lurasidone hydrochloride tablet-treated patients with normal prolactin levels at baseline (n=260) was 6.5 ng/mL compared to 1.4 ng/mL in placebo-treated patients (n=130), and was higher in female patients (7.7 ng/mL) compared to male patients (4.9 ng/mL).
The proportion of patients with prolactin elevations ≥5X upper limit of normal (ULN) was 0.4% for lurasidone hydrochloride tablet-treated patients versus 0.0% for placebo-treated patients. The proportion of female patients with prolactin elevations ≥5X ULN was 0.6% for lurasidone hydrochloride tablet-treated patients versus 0% for placebo-treated female patients. There were no prolactin elevations ≥5X ULN in male patients. The proportion of patients with elevations (≥5X ULN) in prolactin at any post-baseline assessment is shown in Table 28.
Table 28: Proportion of Patients with Elevations (≥5X ULN) in Prolactin (ng/mL) at any Post-baseline Assessment in the Monotherapy Bipolar Depression Study in Adults
| Placebo | Lurasidone Hydrochloride Tablets 20 to 60 mg/ day | Lurasidone Hydrochloride Tablets 80 to 120 mg/ day | |
| All Patients | 0% (n=147) | 0.7% (n=140) | 0% (n=144) |
| Females | 0% (n=82) | 1.3% (n=78) | 0% (n=88) |
Adjunctive Therapy
The median change from baseline to endpoint in prolactin levels, in the short-term, flexible-dose, placebo-controlled adjunctive therapy studies, was 2.8 ng/mL with lurasidone hydrochloride tablets 20-120 mg/day compared to 0.0 ng/mL with placebo-treated patients. The median change from baseline to endpoint for males was 2.4 ng/mL and for females was 3.2 ng/mL. The mean change from baseline to endpoint in prolactin levels in lurasidone hydrochloride tablet-treated patients with normal prolactin levels at baseline (n=291) was 6.2 ng/mL compared to 0.9 ng/mL in placebo-treated patients (n=274), and was higher in female patients (8.4 ng/mL) compared to male patients (3.9 ng/mL). There were no patients with prolactin elevations ≥5X ULN.
Children and Adolescents
In the children and adolescents short-term, placebo-controlled bipolar depression study, the median change from baseline to endpoint in prolactin levels for lurasidone hydrochloride tablet-treated patients was +1.10 ng/mL and was +0.50 ng/mL for placebo-treated patients. For lurasidone hydrochloride tablet-treated patients, the median change from baseline to endpoint for males was +0.85 ng/mL and for females was +2.50 ng/mL. Median changes for prolactin are shown in Table 29.
Table 29: Median Change in Prolactin (ng/mL) from Baseline in the Children and Adolescents Bipolar Depression Study
| Placebo | Lurasidone Hydrochloride Tablets 20 to 80 mg/ day | |
| All Patients | +0.50 (n=157) | +1.10 (n=165) |
| Females | +0.55 (n=78) | +2.50 (n=83) |
| Males | +0.50 (n=79) | +0.85 (n=82) |
The proportion of patients with prolactin elevations ≥5X ULN was 0% for lurasidone hydrochloride tablet-treated patients versus 0.6% for placebo-treated patients. The proportion of female patients with prolactin elevations ≥5X ULN was 0% for lurasidone hydrochloride tablet-treated patients versus 1.3% for placebo-treated female patients. The proportion of male patients with prolactin elevations ≥5X ULN was 0% for lurasidone hydrochloride tablet-treated patients versus 0% for placebo-treated male patients.
Creatinine:
Schizophrenia
Adults
In short-term, placebo-controlled trials, the mean change from baseline in creatinine was 5.3 mcmol/L for lurasidone hydrochloride tablet-treated patients compared to 1.7 mcmol/L for placebo-treated patients. A creatinine shift from normal to high occurred in 3.0% (43/1453) of lurasidone hydrochloride tablet-treated patients and 1.6% (11/681) on placebo. The mean changes from baseline and the proportion of shifts to high generally increased with increased lurasidone doses (Table 30). The threshold for high creatinine values varied from >70 to >115 mcmol/L based on the centralized laboratory definition for each study [see DOSAGE AND ADMINISTRATION and WARNINGS AND PRECAUTIONS, Special Populations].
Table 30: Change in Creatinine from Baseline to Last Study Assessment in Pooled Short-term Studies in Adults
| Placebo | Lurasidone Hydrochloride Tablets 20 mg/day | Lurasidone Hydrochloride Tablets 40 mg/day | Lurasidone Hydrochloride Tablets 80 mg/day | Lurasidone Hydrochloride Tablets 120 mg/day | Lurasidone Hydrochloride Tablets 160 mg/day | ||||||||||||||
| Mean Change from Baseline (mcmol/L) | |||||||||||||||||||
| N=681 | n=71 | n=478 | n=506 | n=283 | n=115 | ||||||||||||||
| Creatinine | 1.8 | 2.7 | 3.5 | 4.4 | 6.2 | 8.8 | |||||||||||||
| Proportion of Patients with Shifts from Normal to Abnormal | |||||||||||||||||||
| Creatinine | 1.6% (11/681) | 1.4% (1/71) | 1.9% (9/478) | 2.2% (11/506) | 4.9% (14/283) | 7.0% (8/115) | |||||||||||||
Adolescents
In the short-term, placebo-controlled study of schizophrenia in adolescent patients (13 to 17 years), the mean change from Baseline in creatinine was -0.796 mcmol/L for lurasidone hydrochloride tablet-treated patients compared to +1.503 mcmol/L for placebo-treated patients. A creatinine shift from normal to high (based on the centralized laboratory definition) occurred in 7.2% (14/194) of lurasidone hydrochloride tablet-treated patients and 2.9% (3/103) on placebo (Table 31).
Table 31: Serum Creatinine Shifts from Normal at Baseline to High at Study End-Point in Adolescent Schizophrenia Study
| Laboratory Parameter | Placebo (N=103) | Lurasidone Hydrochloride Tablets 40 mg/ day (N=97) | Lurasidone Hydrochloride Tablets 80 mg/ day (N=97) |
| Serum Creatinine Elevated | 2.9% | 7.2% | 7.2% |
Bipolar Depression
Adults
Monotherapy
In the short-term, placebo-controlled monotherapy study, the mean change from Baseline in creatinine was 0.9 mcmol/L for lurasidone hydrochloride tablet-treated patients compared to -1.8 mcmol/L for placebo-treated patients. A creatinine shift from normal to high occurred in 2.8% (9/322) of lurasidone hydrochloride tablet-treated patients and 0.6% (1/162) on placebo (Table 32).
Table 32: Change in Creatinine from Baseline to Last Study Assessment in the Monotherapy Bipolar Depression Study in Adults
| Placebo | Lurasidone Hydrochloride Tablets 20 to 60 mg/day | Lurasidone Hydrochloride Tablets 80 to 120 mg/day | |||||||
| Mean Change from Baseline (mcmol/L) | |||||||||
| n=162 | n=161 | n=161 | |||||||
| Creatinine | -1.8 | 0.9 | 1.8 | ||||||
| Proportion of Patients with Shifts from Normal to Abnormal | |||||||||
| Creatinine | 0.6% (1/162) | 1.9% (3/161) | 3.7% (6/161) | ||||||
Adjunctive Therapy
In the short-term, flexible-dose, placebo-controlled adjunctive therapy studies, the mean change from Baseline in creatinine was 3.5 mcmol/L for lurasidone hydrochloride tablet-treated patients compared to -0.9 mcmol/L for placebo-treated patients. A creatinine shift from normal to high occurred in 4.3% (15/348) of lurasidone hydrochloride tablet-treated patients and 1.6% (5/316) on placebo (Table 33).
Table 33: Change in Creatinine from Baseline to Last Study Assessment in the Adjunctive Therapy Bipolar Depression Studies in Adults
| Placebo | Lurasidone Hydrochloride Tablets 20 to 120 mg/day | ||||||
| Mean Change from Baseline (mcmol/L) | |||||||
| n=316 | n=348 | ||||||
| Creatinine | -0.9 | 3.5 | |||||
| Proportion of Patients with Shifts from Normal to Abnormal | |||||||
| Creatinine | 1.6% (5/316) | 4.3% (15/348) | |||||
Children and Adolescents
In the children and adolescents short-term, placebo-controlled bipolar depression study, the mean change from Baseline in serum creatinine was 1.9 mcmol/L for lurasidone hydrochloride tablet-treated patients compared to 0.8 mcmol/L for placebo-treated patients. A creatinine shift from normal to high (based on the centralized laboratory definition) occurred in 6.7% (11/163) of lurasidone hydrochloride tablet-treated patients and 4.5% (7/155) on placebo (Table 34).
Table 34: Change in Creatinine from Baseline to Study Endpoint in the Children and Adolescents Bipolar Depression Study
| Placebo | Lurasidone Hydrochloride Tablets 20 to 80 mg/day | ||||||
| Mean Change from Baseline at Endpoint (mcmol/L) | |||||||
| (n=155) | (n=163) | ||||||
| Creatinine | 0.8 | 1.9 | |||||
| Proportion of Patients with Shifts from Normal to Abnormal at Endpoint | |||||||
| Creatinine | 4.5% (7/155) | 6.7% (11/163) | |||||
Post-Market Adverse Drug Reactions
Hyponatremia has been identified during post-market use of lurasidone hydrochloride tablets.
Atypical antipsychotic drugs, such as lurasidone, have been associated with cases of sleep apnea, with or without concomitant weight gain. In patients who have a history of or are at risk for sleep apnea, Taro-Lurasidone should be prescribed with caution.
Risks of somnambulism (sleep walking) and sleep-related eating disorder have been associated with the use of atypical antipsychotics including lurasidone hydrochloride tablets.
DRUG INTERACTIONS
Overview
Taro-Lurasidone (lurasidone hydrochloride) is contraindicated with strong CYP3A4 inhibitors (e.g., ketoconazole) and strong CYP3A4 inducers (e.g., rifampin) [see CONTRAINDICATIONS]. Taro-Lurasidone should be started at a dose of 20 mg/day, and the dose should not exceed 40 mg/day if coadministered with moderate CYP3A4 inhibitors.
The use of Taro-Lurasidone should be avoided in combination with drugs known to prolong QTc interval or cause electrolyte disturbances [see WARNINGS AND PRECAUTIONS, Cardiovascular, QT Interval].
Drug-Drug Interactions
Potential for Other Drugs to Affect Taro-Lurasidone
Cytochrome P450 enzyme inhibitors or inducers: lurasidone hydrochloride tablets are predominantly metabolized by CYP3A4; interaction of lurasidone hydrochloride tablets with strong and moderate inhibitors or inducers of this enzyme has been observed (Table 35). Taro-Lurasidone is contraindicated in combination with strong inhibitors or inducers of this enzyme [see CONTRAINDICATIONS].
Table 35: Summary of Effect of Coadministered Drugs on Exposure to Lurasidone Hydrochloride Tablets in Healthy Subjects or Patients with Schizophrenia
| Coadministered Drug | Ref | Dose Schedule | Effect on Lurasidone Hydrochloride Pharmacokinetics | Recommendation | |||||
| Coadministered Drug | Lurasidone Hydrochloride Tablets | Cmax | AUC | ||||||
Ketoconazole (strong CYP3A4 inhibitor) | CT | 400 mg/day for 5 days | 10 mg single dose | 6.9-times Lurasidone hydrochloride alone | 9.0-times Lurasidone hydrochloride alone | Contraindicated in combination with Taro-Lurasidone | |||
Diltiazem (moderate CYP3A4 inhibitor) | CT | 240 mg/day for 5 days | 20 mg single dose | 2.1-times Lurasidone hydrochloride alone | 2.2-times Lurasidone hydrochloride alone | Taro-Lurasidonedose should not exceed 40 mg/day if coadministered | |||
Rifampin (strong CYP3A4 inducer) | CT | 600 mg/day for 8 days | 40 mg single dose | 1/7th of Lurasidone hydrochloride alone | 1/5th of Lurasidone hydrochloride alone | Contraindicated in combination with Taro-Lurasidone | |||
| Lithium | CT | 600 mg BID for 8 days | 120 mg/day for 8 days | 0.9-times Lurasidone hydrochloride alone | 1.1-times Lurasidone hydrochloride alone | No Taro-Lurasidonedose adjustment required | |||
Legend: CT = Clinical Trial
Transporter inhibitors: Lurasidone is a substrate of P-gp and BCRP in vitro and the in vivo relevance of this is unclear. Coadministration of lurasidone with P-gp and BCRP inhibitors may increase exposure to lurasidone.
Potential for Taro-Lursidone to Affect Other Drugs
Midazolam (CYP3A4 substrate): Coadministration of lurasidone hydrochloride tablets (120 mg/day) at steady state with a single dose of 5 mg midazolam increased midazolam Cmax and AUC(0-24) by approximately 21% and 44%, respectively, relative to midazolam alone. Midazolam dose adjustment is not required when coadministered with Taro-Lurasidone.
Oral Contraceptive (estrogen/progesterone): Coadministration of lurasidone hydrochloride tablets (40 mg/day) at steady state with an oral contraceptive (OC) containing ethinyl estradiol and norelgestromin resulted in equivalent AUC0-24 and Cmax of ethinyl estradiol and norelgestromin relative to OC administration alone. Also, sex hormone binding globulin levels were not meaningfully affected by coadministration of lurasidone hydrochloride tablets and OC. Dose adjustment of OC dose is not required when coadministered with Taro-Lurasidone.
Transporter substrates: Coadministration of lurasidone hydrochloride tablets (120 mg/day) at steady state with a single 0.25 mg dose of digoxin, a P-gp substrate, increased mean Cmax and AUC(0-24) for digoxin by approximately 9% and 13%, respectively, relative to digoxin alone. Digoxin dose adjustment is not generally required when coadministered with Taro-Lurasidone.
Lurasidone is an in vitro inhibitor of the efflux transporter P-gp and the clinical relevance of intestinal P-gp inhibition cannot be excluded. Concomitant administration of the P-gp substrate dabigatran etexilate may result in increased dabigatran plasma concentrations.
Lurasidone is an in vitro inhibitor of the efflux transporter BCRP and the clinical relevance of intestinal BCRP inhibition cannot be excluded. Concomitant administration of BCRP substrates may result in increases in the plasma concentrations of these substrates.
Drug-Food Interactions
Taro-Lurasidone should be taken with food (at least 350 calories independent of fat content) [see ACTION AND CLINICAL PHARMACOLOGY].
Grapefruit, grapefruit juice, and products containing grapefruit extract should be avoided during treatment with Taro-Lurasidone because of the potential to inhibit CYP3A4.
Drug-Herb Interactions
Interactions with herbal products have not been studied.
Drug-Laboratory Interactions
Interactions with laboratory tests have not been identified.
Drug-Lifestyle Interactions
Alcohol/CNS Drugs
Given the primary CNS effects of Taro-Lurasidone, caution should be used when it is taken in combination with other centrally acting drugs and alcohol.
Smoking Status
Based on in vitro studies utilizing human liver enzymes, lurasidone hydrochloride is not a substrate for CYP1A2; smoking is, therefore, not expected to have an effect on the pharmacokinetics of Taro-Lurasidone.
DOSAGE AND ADMINISTRATION
Dosing Considerations
- Taro-Lurasidone (lurasidone hydrochloride) should be administered with food (at least 350 calories independent of fat content). The Cmax of lurasidone is increased approximately 3-fold and the AUC is increased approximately 2-fold in the presence of food.
- Tablets should not be crushed or cut, they should be swallowed whole.
Recommended Dose and Dosage Adjustment
Schizophrenia
Adults
The recommended starting dose of Taro-Lurasidone is 40 mg once daily. In placebo-controlled clinical trials, once daily doses of 40, 80, 120, and 160 mg were shown to be effective. Patients should be treated with the lowest effective dose that provides optimal clinical response and tolerability, which is expected to be 40 mg or 80 mg once daily for most patients. Doses above 80 mg may be considered for certain patients based on individual clinical judgement.
Doses below 40 mg have not been shown to be effective in patients with schizophrenia.
Adolescents
The recommended starting dose of Taro-Lurasidone is 40 mg once daily. In a placebo-controlled clinical trial, lurasidone hydrochloride tablets have been shown to be effective at doses of 40 mg per day and 80 mg per day. The maximum recommended dose is 80 mg per day. Patients should be treated with the lowest effective dose that provides optimal clinical response and tolerability. In the placebo-controlled clinical trial, no additional benefit was demonstrated for 80 mg over 40 mg.
The safety and efficacy of lurasidone hydrochloride tablets during long term treatment have not been systematically evaluated in adolescent patients with schizophrenia. The physician who elects to use Taro-Lurasidone for extended periods in adolescent patients with schizophrenia should periodically re-evaluate the long term usefulness of the drug for the individual patient.
Bipolar Depression
Adults
The recommended starting dose of Taro-Lurasidone is 20 mg given once daily as monotherapy or as adjunctive therapy with lithium or valproate. In placebo-controlled trials, once daily doses in the range of 20 mg/day to 120 mg/day as monotherapy or as adjunctive therapy with lithium or valproate were studied. In the only study that compared different lurasidone hydrochloride tablet dosage strengths, efficacy of lurasidone hydrochloride tablets were demonstrated in both 20 mg-60mg/day and 80-120 mg/day dosage arms. No additional benefit however, was seen in the higher dose arm [See Part II: CLINICAL TRIALS]. Thus, a usual treatment dose range of 20 mg-60 mg/day as monotherapy or adjunctive therapy with lithium or valproate is recommended. As the incidence of certain adverse events increase with dose [see ADVERSE REACTIONS] patients should be treated with the lowest effective dose of Taro-Lurasidone.
In bipolar depression, the safety of doses above 120 mg/day has not been evaluated. In addition, the efficacy of doses below 20 mg/day has not been studied.
Children and Adolescents (13-17 years of age)
The recommended starting dose of Taro-Lurasidone is 20 mg given once daily as monotherapy. Initial dose titration is not required. The efficacy of lurasidone hydrochloride tablets have been established in a dose range of 20 mg per day to 80 mg per day as monotherapy. The maximum recommended dose is 80 mg per day.
Switching from Other Antipsychotics
There are no systematically collected data to specifically address switching patients from other antipsychotics to lurasidone hydrochloride tablets or concerning concomitant administration with other antipsychotics. While immediate discontinuation of the previous antipsychotic treatment may be acceptable for some patients, more gradual discontinuation may be most appropriate for others. In all cases, the period of overlapping antipsychotic administration should be minimized.
Dosing Considerations for Special Populations
Geriatrics (>65 years of age):
Taro-Lurasidone is not indicated in elderly patients with dementia [see WARNINGS AND PRECAUTIONS, Serious Warnings and Precautions Box and Special Populations ].
The safety and efficacy of lurasidone hydrochloride tablets in patients 65 years of age or older have not been established. Caution should, thus, be exercised with the use of Taro-Lurasidone in the elderly patient, recognizing the more frequent hepatic, renal, central nervous system and cardiovascular dysfunctions, and more frequent use of concomitant medications in this population.
Pediatrics:
Schizophrenia
Safety and efficacy were evaluated in adolescent (13-17 years of age) patients with schizophrenia in one 6-week clinical trial. Taro-Lurasidone is not indicated for the treatment of schizophrenia in adolescent patients under 15 years of age due to insufficient safety and efficacy data [see ADVERSE REACTIONS, CLINICAL TRIALS, Schizophrenia, Adolescents].
Bipolar depression
The safety and efficacy of lurasidone hydrochloride tablets 20 to 80 mg/day for the treatment of bipolar depression in children and adolescents (10 to 17 years) were evaluated in a 6-week, placebo-controlled clinical study in 343 children and adolescents. Taro-Lurasidone is not indicated for the treatment of depressive episodes in bipolar I disorder in patients less than 13 years of age due to insufficient safety and efficacy data [see ADVERSE REACTIONS, CLINICAL TRIALS, Bipolar Depression, Children and Adolescents].
Irritability Associated with Autistic Disorder
Efficacy was not demonstrated in a 6-week study evaluating lurasidone hydrochloride tablets 20 mg/day and 60 mg/day for the treatment of pediatric patients 6 to 17 years of age with irritability associated with autistic disorder.
Gender and Race:
Dosage adjustments are not recommended on the basis of gender or race [see ACTION AND CLINICAL PHARMACOLOGY].
Renal Impairment:
Dose adjustment is recommended in moderate and severe renal impairment patients. Caution should be exercised when starting Taro-Lurasidone in patients with renal impairment. The recommended starting dose is 20 mg. Patients should be treated with the lowest effective dose that provides optimal clinical response and tolerability, which is expected to be 20-40 mg once daily for most patients with moderate or severe renal function impairment. The dose should not exceed 80 mg/day in patients with moderate and severe renal impairment [see ACTION AND CLINICAL PHARMACOLOGY].
Hepatic Impairment:
Dose adjustment is recommended in moderate and severe hepatic impairment patients. Caution should be exercised when starting Taro-Lurasidone in patients with hepatic impairment. The recommended starting dose is 20 mg. Patients should be treated with the lowest effective dose that provides optimal clinical response and tolerability, which is expected to be 20-40 mg once daily for most patients with moderate or severe hepatic impairment (Child Pugh Class B and C). The dose in these patients should not exceed 40 mg/day in patients with severe hepatic impairment, and 80 mg/day in patients with moderate hepatic impairment [see ACTION AND CLINICAL PHARMACOLOGY].
Patients taking Taro-Lurasidone Concomitantly with Potential CYP3A4 Inhibitors:
When coadministration of Taro-Lurasidone with a moderate CYP3A4 inhibitor, such as diltiazem, is considered, Taro-Lurasidone should be started at a dose of 20 mg/day, and the dose should not exceed 40 mg/day. Taro-Lurasidone is contraindicated in combination with a strong CYP3A4 inhibitor (e.g., ketoconazole) [see CONTRAINDICATIONS and DRUG INTERACTIONS].
Patients taking Taro-Lurasidone Concomitantly with Potential CYP3A4 Inducers:
Taro-Lurasidone is contraindicated in combination with a strong CYP3A4 inducer (e.g., rifampin) [see CONTRAINDICATIONS and DRUG INTERACTIONS].
Administration
Taro-Lurasidone should be administered with food (at least 350 calories independent of fat content). The Cmax of lurasidone is increased approximately 3-fold and the AUC is increased approximately 2-fold in the presence of food.
OVERDOSAGE
Human Experience
In pre-marketing clinical studies, accidental or intentional overdosage of lurasidone hydrochloride tablets was identified in one patient who ingested an estimated 560 mg of lurasidone hydrochloride. This patient recovered without sequelae. This patient resumed lurasidone hydrochloride tablet treatment for an additional two months.
Management of Overdosage
There is no specific antidote to Taro-Lurasidone, therefore, appropriate supportive measures should be instituted and close medical supervision and monitoring should continue until the patient recovers.
Cardiovascular monitoring should commence immediately, including continuous electrocardiographic monitoring for possible arrhythmias. If antiarrhythmic therapy is administered, disopyramide, procainamide, and quinidine carry a theoretical hazard of additive QT-prolonging effects when administered in patients with an acute overdose of lurasidone hydrochloride tablets. Similarly the alpha-blocking properties of bretylium might be additive to those of lurasidone hydrochloride tablets, resulting in problematic hypotension.
Hypotension and circulatory collapse should be treated with appropriate measures. Epinephrine and dopamine should not be used, or other sympathomimetics with beta-agonist activity, since beta stimulation may worsen hypotension in the setting of lurasidone hydrochloride tablet-induced alpha blockade. In case of severe extrapyramidal symptoms, anticholinergic medication should be administered.
Gastric lavage (after intubation if patient is unconscious) and administration of activated charcoal together with a laxative should be considered.
The possibility of obtundation, seizures, or dystonic reaction of the head and neck following overdose may create a risk of aspiration with induced emesis.
For management of a suspected drug overdose, contact your regional Poison Control Centre.
ACTION AND CLINICAL PHARMACOLOGY
Mechanism of Action
The mechanism of action of lurasidone, as with other drugs having efficacy in schizophrenia and bipolar depression, is unknown. It has been suggested that the efficacy of lurasidone in schizophrenia and bipolar depression could be mediated through a combination of central dopamine Type 2 (D2) and serotonin Type 2 (5HT2A) receptor antagonism.
Pharmacodynamics
In vitro receptor binding studies revealed that lurasidone is an antagonist with high affinity at dopamine D2 receptors (Ki = 0.994 nM), the 5-hydroxytryptamine (5-HT, serotonin) receptors 5-HT2A (Ki = 0.47 nM), and 5-HT7 (Ki = 0.495 nM); is an antagonist with moderate affinity at α2C adrenergic receptors (Ki = 10.8) and α2A adrenergic receptors (Ki = 40.7 nM), α1 adrenergic receptors (Ki = 47.9 nM) and is a partial agonist with moderate affinity at serotonin 5-HT1A (Ki = 6.38 nM) receptors.. Lurasidone exhibits little or no affinity for histamine H1 and muscarinic M1 receptors (IC50 >1,000 nM).
Pharmacokinetics
Adults
The activity of lurasidone is primarily due to the parent drug. The pharmacokinetics of lurasidone are dose-proportional within a total daily dose range of 20 mg to 160 mg. Steady state concentrations of lurasidone are reached within 7 days of starting lurasidone hydrochloride tablets. Following administration of 40 mg of lurasidone hydrochloride tablets, the mean (%CV) elimination half-life was 18 (7) hours.
Absorption
Lurasidone is absorbed and reaches peak serum concentrations in approximately 1-3 hours. It is estimated that 9-19% of an administered dose is absorbed.
In a food effect study, lurasidone mean Cmax and AUC were about 3-times and 2-times, respectively, when administered with food compared to the levels observed under fasting conditions. Lurasidone exposure was not affected as meal size was increased from 350 to 1000 calories and was independent of meal fat content.
In clinical studies, establishing the safety and efficacy of lurasidone hydrochloride tablets, patients were instructed to take their daily dose with food.
Distribution
Following administration of 40 mg of lurasidone hydrochloride tablets, the mean (%CV) apparent volume of distribution was 6173 (17.2) L. Lurasidone is highly bound (~99%) to serum proteins.
Metabolism
Lurasidone is metabolized mainly via CYP3A4 enzyme. The major biotransformation pathways are oxidative N-dealkylation, hydroxylation of norbornane ring, and S-oxidation. Lurasidone is metabolized into two active metabolites (ID-14283 and ID-14326) and two major non-active metabolites (ID-20219 and ID-20220).
Excretion
Total excretion of radioactivity in urine and feces combined was approximately 89%, with about 80% recovered in feces and 9% recovered in urine, after a single dose of [14C]-labeled lurasidone
Following administration of 40 mg of lurasidone hydrochloride tablets, the mean (%CV) apparent clearance was 3902 (18.0) mL/min.
Adolescents
The pharmacokinetics of lurasidone in child and adolescent patients (10 to 17 years of age) were similar to those in adults. There were no clinically relevant differences between genders in the pharmacokinetics of lurasidone in patients with schizophrenia and bipolar I disorder.
Transporter Proteins
Lurasidone is an in vitro substrate of the efflux transporters P-gp and BCRP. Lurasidone is not subject to active uptake transport by OATP1B1 or OATP1B3.
Lurasidone is an inhibitor of P-gp, BCRP and OCT1 in vitro. Lurasidone is not expected to have a clinically relevant inhibitory potential on transporters OATP1B1, OATP1B3, OCT2, OAT1, OAT3, MATE1, MATE2K or BSEP based on in vitro data.
Special Populations and Conditions
Geriatrics
In elderly patients with psychosis (65 to 85), lurasidone concentrations (20 mg/day) were, on average, similar to those in young subjects [see also WARNINGS AND PRECAUTIONS, Special Populations, Geriatrics].
Gender
Population pharmacokinetic evaluation indicated that the mean AUC of lurasidone hydrochloride tablets was 18% higher in women than in men, and correspondingly, the apparent oral clearance of lurasidone hydrochloride tablets was lower in women. Mean Cmax of lurasidone hydrochloride tablets was similar between women and men. No dosage adjustment is recommended based on gender.
Race
Although no specific pharmacokinetic study was conducted to investigate the effects of race on the disposition of lurasidone hydrochloride tablets, population pharmacokinetic evaluation revealed no evidence of clinically significant race-related differences in the pharmacokinetics of lurasidone hydrochloride tablets. No dosage adjustment is recommended based on race.
Hepatic Insufficiency
Dose adjustment is recommended in patients with moderate or severe hepatic impairment. The recommended starting dose is 20 mg. Patients should be treated with the lowest effective dose that provides optimal clinical response and tolerability, which is expected to be 20-40 mg once daily for most patients with moderate or severe hepatic impairment (Child Pugh Class B and C). The dose should not exceed 40 mg/day in patients with severe hepatic impairment (Child-Pugh Class C), and 80 mg/day in patients with moderate hepatic impairment (Child-Pugh Class B). In a single-dose study of lurasidone hydrochloride tablets 20 mg, lurasidone AUC0-last was 1.5-times higher in subjects with mild hepatic impairment (Child-Pugh Class A), 1.7-times higher in subjects with moderate hepatic impairment (Child-Pugh Class B), and 3-times higher in subjects with severe hepatic impairment (Child-Pugh Class C) compared to the values for healthy matched subjects. Mean Cmax was 1.3, 1.2, and 1.3-times higher for mild, moderate, and severe hepatically impaired patients, respectively, compared to the values for healthy matched subjects.
Renal Insufficiency
Dose adjustment is recommended in patients with moderate or severe renal function impairment. The recommended starting dose is 20 mg. Patients should be treated with the lowest effective dose that provides optimal clinical response and tolerability, which is expected to be 20-40 mg once daily for most patients with moderate and severe renal impairment (Clcr ≥10 mL/min to <50 mL/min). The dose should not exceed 80 mg/day in patients with moderate and severe renal impairment. After administration of a single dose of 40 mg lurasidone hydrochloride tablet to patients with mild, moderate, and severe renal impairment, mean Cmax increased by 40%, 92%, and 54%, respectively, and mean AUC(0-∞) increased by 53%, 91%, and 2- times, respectively, compared to healthy matched subjects.
Smoking Status
Based on in vitro studies utilizing human liver enzymes, lurasidone hydrochloride is not a substrate for CYP1A2; smoking is therefore not expected to have an effect on the pharmacokinetics of Taro-Lurasidone.
STORAGE AND STABILITY
Store Taro-Lurasidone (lurasidone hydrochloride) tablets at 15° - 30°C.
SPECIAL HANDLING INSTRUCTIONS
None.
DOSAGE FORMS, COMPOSITION AND PACKAGING
Taro-Lurasidone (lurasidone hydrochloride) tablets are white to off-white, round (20 mg and 40 mg), white to off-white, capsule shaped (60 mg), pale green, oval (80 mg), or white to off-white, oval (120 mg) and identified with strength-specific one-sided debossing, “578” (20 mg), “684” (40 mg), “639” (60mg), “685” (80 mg), or “579” (120 mg).
Each tablet contains 20 mg, 40 mg, 60 mg, 80 mg, or 120 mg of lurasidone hydrochloride. Inactive ingredients are mannitol, alginic acid, pregelatinized starch, croscarmellose sodium, colloidal silica, magnesium stearate, 20mg, 40 mg 60 mg and 120mg additionally contains opadry white (hypromellose, titanium dioxide, macrogol, carnauba wax), whereas 80 mg tablet contains opadry green (hypromellose, titanium dioxide, macrogol, iron oxide yellow, carnauba wax, FD&C blue #1 and ferrosoferric oxide).
Tablets are supplied in bottles of 30, 90 and 500 tablets and boxes of 30 (3 blister cards, 10 tablets each).
PART II: SCIENTIFIC INFORMATION
PHARMACEUTICAL INFORMATION
Drug Substance
Proper name: lurasidone hydrochloride
Chemical name: (3aR,4S,7R,7aS)-2-{(1R,2R)-2-[4-(1,2-benzisothiazol-3-yl)piperazin-1-ylmethyl]cyclohexylmethyl}hexahydro-4,7-methano-2H-isoindole-1,3-dione hydrochloride
Molecular formula and molecular mass: C28H36N4O2S·HCl
M.W: 529.14 g / mol
Structural formula:
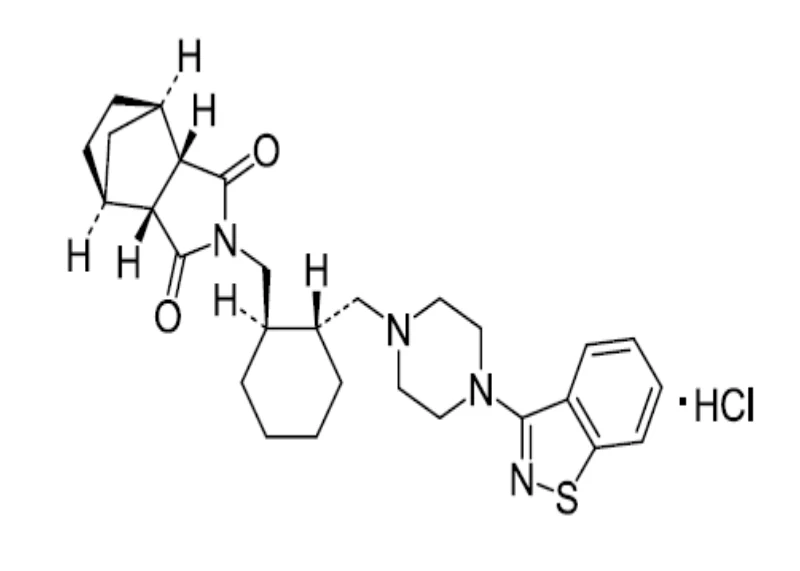
Physicochemical properties: White to off-white powder
Very slightly soluble in water
Practically insoluble or insoluble in 0.1 N HCl
Slightly soluble in ethanol
Sparingly soluble in methanol
Practically insoluble or insoluble in toluene
Very slightly soluble in acetone
CLINICAL TRIALS
A randomized, blinded, two-treatment, two-sequence, two-period, single-dose (1 x 40 mg), crossover comparative bioavailability study comparing Taro-Lurasidone (lurasidone hydrochloride) tablets 40 mg (Taro Pharmaceuticals Inc.) with Latuda® tablets 40 mg (Sunovion Pharmaceuticals Canada Inc.) was conducted in 40 healthy, adult, male subjects under fed conditions. Comparative bioavailability data from 31 subjects that were included in the statistical analysis are presented in the following table.
SUMMARY TABLE OF THE COMPARATIVE BIOAVAILABILITY DATA
Lurasidone (1 x 40 mg lurasidone hydrochloride) Geometric Mean Arithmetic Mean (CV %) | ||||
|---|---|---|---|---|
| Parameter | Test* | Reference† | % Ratio of Geometric Means | 90% Confidence Interval |
AUC0-72h (ng.h/mL) | 417.72 449.46 (37.64) | 427.83 453.61 (33.57) | 96.75 | 92.29 - 101.42 |
AUCI (ng.h/mL) | 451.21 486.31 (38.25) | 472.34 500.32 (33.23) | 96.3 | 91.7 - 101.2 |
Cmax (ng/mL) | 91.33 98.65 (37.24) | 98.30 107.82 (44.44) | 91.8 | 83.1 - 101.5 |
Tmax§ (h) | 2.00 (1.00 -5.00) | 2.00 (1.00 - 5.00) | ||
T½€ (h) | 34.01 (38.84) | 36.58 (29.76) | ||
* Taro-Lurasidone (lurasidone hydrochloride) tablet 40 mg (Taro Pharmaceuticals Inc.)
† Latuda® (lurasidone hydrochloride) tablet 40 mg (Sunovion Pharmaceuticals Canada Inc.)
§ Expressed as the median (range)
€ Expressed as the arithmetic mean (CV%)
Schizophrenia
Adults
Study Demographics and Trial Design
The efficacy of lurasidone hydrochloride tablets for the treatment of schizophrenia was established in five short-term (6-week), placebo-controlled studies in adult patients (mean age of 38.4 years, range 18-72) who met DSM-IV criteria for schizophrenia. An active control arm (olanzapine or quetiapine XR) was included in two studies to assess assay sensitivity; the studies were not designed to compare lurasidone hydrochloride tablets to the active comparators. In four of the five short-term studies, the study drug was administered once daily in the morning with a meal or within 30 minutes after eating, although evening dosing was permitted with Medical Monitor approval. In the fifth study, comparing lurasidone hydrochloride tablets 80 mg and 160 mg doses and quetiapine XR 600 mg dose to placebo, the study drug was administered once daily in the evening with a meal or within 30 minutes after eating and efficacy and safety assessments were performed the next morning.
In two additional short-term (6-week), placebo-controlled studies, neither lurasidone hydrochloride tablets (20 mg, 40 mg, or 80 mg) nor the active comparators (haloperidol 10 mg/day or risperidone 4 mg/day) showed superiority to placebo in the primary efficacy outcome, and thus were considered failed studies.
Several instruments were used for assessing psychiatric signs and symptoms in these studies:
- 1. Positive and Negative Syndrome Scale (PANSS) is a multi-item inventory of general psychopathology used to evaluate the effects of drug treatment in schizophrenia. PANSS total scores may range from 30 to 210.
- 2. Brief Psychiatric Rating Scale derived (BPRSd), derived from the PANSS, is a multi-item inventory primarily focusing on positive symptoms of schizophrenia, whereas the PANSS includes a wider range of positive, negative, and other symptoms of schizophrenia. BPRSd scores may range from 18 to 126.
- 3. The Clinical Global Impression severity scale (CGI-S) is a validated clinician-rated scale that measures the subject’s current illness state on a 1 to 7-point scale.
The endpoint associated with each instrument is change from baseline in the total score to the end of week 6. These changes are then compared to placebo changes for the drug and control groups.
Study Results
The results of the positive studies follow:
- 1. In a 6-week, placebo-controlled trial (N=145) involving two fixed doses of lurasidone hydrochloride tablets (40 or 120 mg/day), both doses of lurasidone hydrochloride tablets at Endpoint were superior to placebo on the BPRSd total score and the CGI-S score.
- 2. In a 6-week, placebo-controlled trial (N=180) involving a fixed dose of lurasidone hydrochloride tablets (80 mg/day), lurasidone hydrochloride tablets at Endpoint was superior to placebo on the BPRSd total score and the CGI-S score.
- 3. In a 6-week, placebo and active-controlled trial (N=473) involving two fixed doses of lurasidone hydrochloride tablets (40 or 120 mg/day) and an active control (olanzapine) to assess study assay sensitivity, both lurasidone hydrochloride tablet doses and the active control at Endpoint were superior to placebo on the PANSS total score and the CGI-S score.
- 4. In a 6-week, placebo-controlled trial (N=489) involving three fixed doses of lurasidone hydrochloride tablets (40, 80, or 120 mg/day), only the 80 mg/day dose of lurasidone hydrochloride tablets at Endpoint was superior to placebo on the PANSS total score and the CGI-S score.
- 5. In a 6-week, placebo, and active-controlled trial (N=482) involving two fixed doses of lurasidone hydrochloride tablets (80 or 160 mg/day) and an active control (quetiapine XR) to assess study assay sensitivity, both lurasidone hydrochloride tablet doses and the active control at Endpoint were superior to placebo on the PANSS total score and the CGI-S score.
Adolescents
The efficacy of lurasidone hydrochloride tablets in the treatment of schizophrenia in adolescent patients (13 to 17 years of age) was evaluated in one 6-week, placebo-controlled study of patients (N=326) who met DSM-IV criteria for schizophrenia. The majority of patients (72%) included in the trial were 15 to 17 years of age.
Patients were randomized to placebo or fixed doses of lurasidone hydrochloride tablets (40 mg or 80 mg). The primary efficacy endpoint was the change from Baseline in the Positive and Negative Syndrome Scale (PANSS) Total Score at Week 6.
Both the 40 mg and 80 mg doses of lurasidone demonstrated superiority over placebo on the PANSS total score after 6 weeks of double-blind treatment (Table 36). The 80 mg dose was not shown to be more efficacious than the 40 mg dose.
Table 36: Primary Efficacy Results for Study in Adolescent Schizophrenia (PANSS
Total Score)
Primary Efficacy Measure: PANSS Placebo-
Treatment Group
Mean Baseline
Score (SD)
LS Mean Change
from Baseline
(SE)
subtracted Differencea (95% CI)
| Lurasidone hydrochloride tablets (40 mg/day)* | 94.5 ( | 10.97) | -18.6 ( 1.59) | -8.0 (-12.4, -3.7) | |
| Lurasidone hydrochloride tablets (80 mg/day)* | 94.0 ( | 11.12) | -18.3 ( 1.60) | -7.7 (-12.1, -3.4) | |
| Placebo | 92.8 ( | 11.08) | -10.5 ( 1.59) | -- | |
SD: standard deviation; SE: standard error; LS Mean: least-squares mean; CI: confidence interval, unadjusted for multiple comparisons. a Difference (drug minus placebo) in least-squares mean change from baseline. * Doses statistically significantly superior to placebo. | |||||
Bipolar Depression
Adults
Study Demographics and Trial Design
Monothe rapy
The efficacy of lurasidone hydrochloride tablets, as monotherapy, was established in a 6-week, randomized, double- blind, placebo-controlled study of adult patients (mean age of 41.5 years, range 18-74) who met DSM-IV-TR criteria for depressive episodes associated with bipolar I disorder, with or without rapid cycling, and without psychotic features (N=485). Patients were randomized to flexibly dosed lurasidone hydrochloride tablets 20-60 mg/day, lurasidone hydrochloride tablets 80-120 mg/day or placebo. Primary and key secondary efficacy assessments were conducted at baseline and Weeks 1 through 6.
The primary rating instrument used to assess depressive symptoms in this study was the Montgomery-Asberg Depression Rating Scale (MADRS), a 10-item clinician-rated scale with total scores ranging from 0 (no depressive features) to 60 (maximum score). The primary endpoint was the change from baseline in MADRS score at Week 6. The key secondary instrument was the Clinical Global Impression-Bipolar-Severity of Illness scale (CGI-BP-S), a clinician-rated scale that measures the subject’s current illness state on a 7-point scale, where a higher score is associated with greater illness severity.
Adjunctive Therapy
The efficacy of lurasidone hydrochloride tablets, as an adjunctive therapy to lithium or valproate, was evaluated in two (N=340 and 342) 6-week, randomized, double-blind, placebo-controlled studies of adult patients (mean age of 42.6 years, range 18-74) who met DSM-IV-TR criteria for depressive episodes associated with bipolar I disorder, with or without rapid cycling, and without psychotic features. Patients who remained symptomatic during treatment with lithium or valproate were randomized to flexibly dosed lurasidone hydrochloride tablets 20-120 mg/day or placebo. Primary and key secondary efficacy assessments were conducted at baseline and Weeks 1 through 6.
The primary rating instrument used to assess depressive symptoms in this study was the MADRS. The primary endpoint was the change from baseline in MADRS score at Week 6. The key secondary instrument was the CGI-BP-S scale.
Study Results
Monotherapy
Lurasidone hydrochloride tablets were superior to placebo in reduction of MADRS and CGI-BP-S scores at Week 6. The high dose group (80-120 mg) did not provide improved efficacy on average compared to the low dose group (20-60 mg). Significant treatment differences in MADRS and CGI-BP-S were observed at Week 2 for lurasidone hydrochloride tablets 20-60 mg which were sustained for the remainder of the study. The proportion of patients with ≥ 50% improvement in MADRS was significantly greater (p<0.001) in both lurasidone hydrochloride tablet flexible-dose groups (53% lurasidone hydrochloride tablets 20-60 mg; 51% lurasidone hydrochloride tablets 80-120 mg) vs. placebo (30%). Both lurasidone hydrochloride tablet dose groups were associated with significantly greater improvement than placebo on seven of the 10 MADRS items (p<0.05). The secondary endpoints supported the superiority of lurasidone hydrochloride tablets over placebo.
Adjunctive Therapy
In one study, lurasidone hydrochloride tablets were superior to placebo in reduction of MADRS and CGI-BP-S scores as an adjunctive therapy to lithium or valproate at Week 6. Significant treatment differences were observed in the lurasidone hydrochloride tablets + lithium or valproate dose group at Week 3 in MADRS and at Week 2 in the CGI-BP-S which were sustained for the remainder of the study. The proportion of patients with ≥ 50% improvement in MADRS was significantly greater (p=0.008) in the lurasidone hydrochloride tablets + lithium or valproate dose group (57%) vs. placebo (42%). Lurasidone hydrochloride tablets were associated with significantly greater improvement than placebo on six of the 10 MADRS items (p<0.05). The secondary endpoints supported the superiority of lurasidone hydrochloride tablets over placebo.
In a second study, a statistically significant difference was not demonstrated between lurasidone hydrochloride tablets and placebo for the primary endpoint (MADRS) at Week 6.
Children and Adolescents
The efficacy of lurasidone hydrochloride tablets was evaluated in a 6-week, multicenter, randomized, double-blind, placebo-controlled study of children and adolescents (10 to 17 years) who met DSM-V criteria for major depressive episodes associated with bipolar I disorder, with or without rapid cycling, and without psychotic features (N=343). The majority (78%) of patients were 13 years of age or older. Patients were randomized to flexibly dosed lurasidone hydrochloride 20 to 80 mg/day or placebo.
The primary rating scale used to assess depressive symptoms in this study was the Children’s Depression Rating Scale, Revised (CDRS-R) total score. The primary endpoint was the change from baseline in CDRS-R score at Week 6.
Lurasidone hydrochloride tablets were superior to placebo in reduction of CDRS-R total score at Week 6. The primary efficacy results are provided in Table 37.
Table 37: Primary Efficacy Results for the Children and Adolescents Study in
Depressive Episodes Associated with Bipolar I Disorder (CDRS-R Total
Score)
| Treatment Group | Primary Efficacy Measure: CDRS-R | |||||||
Mean Baseline Score (SD) | LS Mean Change from Baseline (SE) | Placebo- subtracted Differencea (95% CI) | ||||||
| Lurasidone hydrochloride tablets (20 to 80 mg/day)* | 59.2 (8.24) | -21.0 (1.06) | -5.7 (-8.4,-3.0) | |||||
| Placebo | 58.6 (8.26) | -15.3 (1.08) | -- | |||||
SD: standard deviation; SE: standard error; LS Mean: least-squares mean; CI: confidence interval, unadjusted for multiple comparisons. a Difference (drug minus placebo) in least-squares mean change from baseline. * Treatment group statistically significantly superior to placebo. | ||||||||
DETAILED PHARMACOLOGY
Nonclinical Pharmacodynamics
Receptor Binding
In vitro receptor binding studies revealed that lurasidone is an antagonist with high affinity at dopamine D2 receptors (Ki = 0.994 nM), D2L receptors (Ki = 0.329 and 0.994 nM), and the 5-hydroxytryptamine (5-HT, serotonin) receptors 5-HT2A (Ki = 0.47 nM) and 5-HT7 (Ki = 0.495 nM), is an antagonist with moderate affinity at human α2C adrenergic receptors (Ki = 10.8 nM), is a partial agonist at serotonin 5-HT1A (Ki = 6.38 nM) receptors, and is an antagonist at α2A adrenergic receptors (Ki = 40.7 nM). Lurasidone exhibits little or no affinity for histamine H1 and muscarinic M1 receptors (IC50 > 1,000 nM).
Schizophrenia
Pharmacological studies have shown that lurasidone was effective in various animal models of schizophrenia induced by methamphetamine or tryptamine, and confirmed its potent dopamine D2-blocking and serotonin 5-HT2-blocking actions.
Bipolar Depression
Pharmacological studies have shown that lurasidone was effective in some animal models of depression.
Effects on the Central Nervous System
Lurasidone, when intravenously administered at high doses, slowed spontaneous electroencephalogram (EEG) in rabbits, and inhibited emetic response in apomorphine-treated dogs following oral administration, but exerted no other potent effects on the CNS (anti-acetylcholine action, anti-hypoxic action, effects on cerebral blood flow, convulsion facilitating action, and anti-adrenergic action).
Lurasidone demonstrated mild anti-histamine and anti-noradrenaline effects but not anti-acetylcholine effect in in vitro studies.
Effects on Cardiovascular System
In addition to the animal studies of antipsychotic efficacy and mechanism of action, a safety pharmacological evaluation of lurasidone was conducted to obtain a more extensive characterization of its actions on various organ systems in vitro and in vivo. Potential cardiovascular effects were assessed in in vitro and in vivo safety pharmacology and toxicology studies. In HEK293 cells stably expressing the hERG gene, lurasidone and its metabolites, ID-14326 and ID-14283, caused concentration-dependent suppression of hERG currents with IC50 values of 57 ng/mL, 357 ng/mL, and 434 ng/mL, respectively. There were no effects on action potential duration (APD) in guinea pig papillary muscle and on inotropic/chronotropic action in guinea pig atrium.
Conscious telemetered female dogs (N=4/treatment) received single oral doses of vehicle, lurasidone 100 mg/kg, lurasidone 300 mg/kg, or sotalol according to Latin square crossover design. Lurasidone 100 mg/kg and 300 mg/kg caused statistically significant increases in heart rate. Lurasidone 300 mg/kg also caused a statistically significant increase in the QTc interval. Cmax values were reported to be 1.9 mcg/mL for lurasidone 100 mg/kg and 2.8 mcg/mL for lurasidone 300 mg/kg. In a 39-week, repeated oral doses toxicology study in dogs, lurasidone showed QTc prolongation in 1 out of 4 male dogs in the 100 mg/kg group and 2 out of 4 male dogs in the 200 mg/kg group. QT prolongation effect of lurasidone in dogs arises at 12- to 20-fold higher plasma levels than the plasma Cmax associated with the maximum dose evaluated in clinical trials.
Nonclinical Pharmacokinetics
The pharmacokinetic parameters (absorption, distribution, metabolism, and excretion) of lurasidone have been studied in mice, rats, dogs, rabbits, and monkeys.
Lurasidone is rapidly absorbed with peak systemic exposure occurring within 5.3 hours of administration. The absolute bioavailability is low, <12%, in all species examined. Administration of lurasidone with food increases the extent of absorption two- to three-fold. Clearance ranged from 17 to 61 mL/min/kg and volume of distribution ranged from 2.4 to 20 L/kg. Terminal elimination half-life is also variable, ranging from 1.6 to 27 hours.
Lurasidone binds extensively (>99% bound) to serum proteins including human serum albumin and α-glycoprotein. Distribution into red blood cells is moderate with blood:plasma ratios ranging from 0.57 – 0.80. Lurasidone distributes into most tissues including the brain and into the fetus.
Lurasidone is extensively metabolized with oxidative N-dealkylation, hydroxylation of the norbornane ring or cyclohexane ring, S-oxidation, reductive cleavage of the isothiazole ring followed by S-methylation, and a combination of two or more of these pathways. Although many metabolites were found in human serum, all primary metabolites were detected in one or more of the nonclinical animal species; therefore, no human specific metabolites have been identified.
The primary metabolizing Cytochrome P450 (CYP) isozyme in humans is CYP3A4. Specific metabolizing isozymes in nonclinical species have not been identified. In vitro studies conducted with human tissue preparations suggest that at clinically relevant concentrations lurasidone does not inhibit or induce CYP enzyme activity. The potential for protein-based clinical drug-drug interactions appears to be minimal as no displacement of lurasidone or co-incubated drugs from serum proteins is observed in vitro. Lurasidone is an in vitro substrate of P-glycoprotein (P-gp) and BCRP, and an inhibitor of P-gp, BCRP and OCT1 in vitro.
Following administration of [14C]lurasidone, the majority of the radioactivity was excreted in feces as parent compound. Approximately 12-48% of the orally administered dose was absorbed. Unchanged parent compound is detected only at trace levels in bile and urine, indicating that the absorbed material is subject to extensive metabolism. Lurasidone is excreted into rat milk primarily as unchanged drug at concentrations that are greater than those in serum.
TOXICOLOGY
Single-Dose Toxicity
In single-dose studies performed in rats and monkeys, there were no deaths at the highest dose levels of 2000 mg/kg in either species. The target organ for acute toxicity is the CNS. Clinical signs in rats consisted of decreased spontaneous activity, ptosis, and decreased body weight and/or body weight gain at ≥1000 mg/kg and ataxic gait at 2000 mg/kg. Treatment-related clinical signs in monkeys included decrease of spontaneous activity in all treated groups (10 to 2000 mg/kg), tremor, and decrease of spontaneous activity accompanied by extrapyramidal symptoms such as persistent abnormal posture and slow movement at 50 mg/kg or higher, closed eyelids at 250 mg/kg, and miosis, closed eyelids, and vomiting at 2000 mg/kg. Food consumption was reduced at 250 mg/kg or higher.
Serum concentrations of lurasidone and prolactin were evaluated after a single oral dose of lurasidone at levels up to 1000 mg/kg in rats. The concentrations of serum prolactin at one (peak level) and two hours after administration, at almost all doses of 10 mg/kg and above, were significantly higher (up to 44-fold control levels) or tended to be higher than the control values, with little or no dose dependency. The increases in peak serum levels and total exposure of lurasidone were dose-dependent up to 500 mg/kg in male rats and up to 1000 mg/kg in female rats.
Repeat-Dose Toxicity
Repeat-dose toxicity studies from 2 to 52 weeks in duration were performed in mice, rats, dogs, and monkeys.
Toxic responses to orally administered lurasidone were rapid in onset. The main target organs of toxicity are the CNS and the endocrine system. Like other antipsychotic drugs that bind to dopamine D2 receptors, lurasidone has been shown to elevate serum prolactin levels in mice, rats, dogs, and monkeys.
Clinical signs evident after repeated doses included decreased spontaneous activity and extrapyramidal effects in rats, dogs, and monkeys. Prolactin-related effects were similar in rodents and dogs regarding histopathologic changes in the mammary glands. Mild signs of mammary development (1 female) and lactogenesis (1 female) were observed in monkeys. Prostatic changes were observed only in dogs, vaginal changes were observed only in rodents, whereas pituitary changes were seen in rodents and monkeys. Prolactin-related fatty infiltration into bone marrow and reduced bone density were seen in rats, but were not observed in mice. Similar changes were seen in a few high-dose dogs that were suffering from emaciation, but which were considered secondary effects of increased corticosteroid secretion in response to the stress of their condition.
Cardiac effects were not determined in the mouse and rat, and were not seen in the monkey at any dose level, but QT prolongation and/or PVC were observed in the dog toxicology studies. Signs of anemia were observed in the 4-week dog study but not in the 39-week study. Except for some of the effects on bone, these clinical signs resolved upon withdrawal of treatment and are considered to represent exaggerated pharmacology of the drug, relating mostly to hyperprolactinemia, or CNS and cardiovascular effects, all commonly seen with D2 receptor antagonist antipsychotic agents. The dosing regimens used in the various repeated-dose studies consisted of once-daily administration by oral gavage in mice, rats, and dogs, and by intranasal gastric gavage in monkeys. In each case the vehicle was 0.5% aqueous methylcellulose.
Mouse Study
All dose levels in the 3-month mouse study (25 to 500 mg/kg/day) produced adverse effects, consisting mainly of decreased spontaneous activity, and effects on female sex organs that were attributed to increased prolactin levels. The NOAEL is less than 25 mg/kg/day for repeated dosing in this species, and the corresponding safety margins for these effects, relative to man at the MRHD of 160 mg/day, are less than 0.38 (males) or less than 0.64 (females) from comparisons based upon peak serum exposure levels of lurasidone, and less than 0.37 (males) or less than 0.60 (females) based upon total serum exposure levels of lurasidone.
Rat Studies
The 90-day NOAEL in male and female rats is 0.3 and 0.1 mg/kg/day, respectively, based upon the combined results of the two 3-month studies performed in Sprague-Dawley rats. The safety margins, based upon peak serum levels relative to man at the MRHD, are 0.005 and 0.001, respectively. Based upon the results of the 6-month study, the NOAEL in rats of either sex is
0.03 mg/kg/day. Dosage administration at levels at or above 1 mg/kg/day for 6 months produced changes in male mammary glands and elevated hemoglobin concentrations, along with elevated prolactin levels. Adverse effects seen in females at these same dose levels included effects on female sex organs and increased incidence of fatty infiltration into the femur marrow, thickened zona glomerulosa of adrenal, and decreased total bone mineral density of femur. The resultant safety margin, based upon peak serum levels relative to man at the MRHD, are 0.0006 and 0.0003, for males and females, respectively.
Dog Studies
All dose levels in both the 4-week and 39-week repeated-dose studies in the Beagle dog produced adverse effects attributed to increased prolactin levels. Both studies utilized 30 mg/kg/day as the lowest dose. In the 4-week study, a 30 mg/kg/day dose produced effects in the thymus and mammary glands. The same dose level in the 39-week study also produced effects on the thymus in males, but more severe mammary effects as well as changes in the uterus and ovary in females and in the prostate of males. All dose levels produced CNS effects (decreased spontaneous activity, tremors, miosis, and somnolence). Thymic atrophy or involution were seen in both dog studies, and increased total cholesterol and phospholipids as well as increased cytoplasmic eosinophilic granule epithelium in urinary bladder were observed at or above 30 mg/kg/day in the 39-week study. The NOAEL is less than 30 mg/kg/day for repeated dosing of lurasidone in the dog, and the corresponding safety margins for these effects, relative to man at the MRHD of 160 mg/day, are less than 3.4 (4 weeks) or less than 4.9 (39 weeks) based upon peak serum levels of lurasidone and less than 3.1 (4 weeks) or less than 11/9.2 (M/F, 39 weeks) based upon total exposure levels.
Monkey Studies
There were no significant prolactin-related adverse effects in the 3-month and 1-year repeated-dose studies in Cynomolgus monkeys. The observations of decreased spontaneous activity, movement disorder, and abnormal posture were considered CNS effects and not directly related to prolactin levels. The only minor finding that was possibly related to prolactin was the presence of enlarged pale staining cells in the pituitary, which were observed upon histopathologic examination in both sexes at 50 mg/kg/day in the 1-year study. Mean serum prolactin concentrations at 4 hours after dosing were increased in a dose-related fashion in all treated groups in both studies.
If one considers the elevation of prolactin levels as a non-adverse effect, the CNS effects observed at 10 and 2 mg/kg/day in the 3-month and 1-year monkey studies, respectively, put the NOAEL for monkeys near 2 mg/kg/day. Safety margins (1-year study) at the MRHD were 0.01 to 0.03 (based on Cmax) and 0.02 to 0.03 (based on AUC).
Reproductive and Developmental Toxicity
Lurasidone was administered orally to female rats at doses of 0.1, 1.5, 15, or 150 mg/kg/day for 15 consecutive days prior to mating, during the mating period, and through day 7 of gestation. Estrus cycle irregularities were seen at 1.5 mg/kg and above; the no-effect dose of 0.1 mg/kg is approximately 0.006 times the maximum recommended human dose (MRHD) of 160 mg/day based on body surface area. Fertility was reduced only at the highest dose and this was shown to be reversible after a 14 day drug-free period. The no-effect dose for reduced fertility was 15 mg/kg, which is 0.9 times the MRHD based on body surface area.
Fertility was not affected in male rats treated orally with lurasidone for 64 consecutive days prior to mating and during the mating period at doses up to 150 mg/kg/day (9 times the MRHD based on body surface area).
No teratogenic effects were seen in studies in which pregnant rats and rabbits were given lurasidone during the period of organogenesis at doses up to 25 and 50 mg/kg/day, respectively. These doses produced plasma levels (AUC) 3.7 and 0.6 times, in rats and rabbits, respectively, the MRHD based upon total exposure.
No adverse developmental effects were seen in a study in which pregnant rats were given lurasidone during the period of organogenesis and continuing through weaning at doses up to 10 mg/kg/day; this dose produced plasma levels (AUC) 1.3 times those in humans receiving the MRHD.
Juvenile Animal Studies
Lurasidone oral administration to juvenile rats at doses of 3, 30, and 150 (males) or 300 (females) mg/kg/day which are 0.7 to 22 times (males) and 0.6 to 63 times (females) plasma levels (AUC) in pediatric/adolescent patients receiving the MRHD of 80 mg/day, from postnatal day (PND) 21 through PND 91 (the period corresponding to childhood, adolescence, and young adulthood) resulted in growth and developmental delays in both genders at 30 mg/kg/day and higher.
The NOAEL for juvenile rats’ physical growth and development is 3 mg/kg/day (0.7 times (males) and 0.6 times (females) the MRHD based upon total exposure. Lurasidone effects included dose-dependent decreases in tibial length, bone mineral content, body and brain weights starting at 30 mg/kg/day in both sexes, and delay in attainment of sexual maturity in males at 150 mg/kg/day and in females starting at 30 mg/kg/day. The delay in attainment of sexual maturity in females was associated with decreased serum estradiol and may have been also exacerbated by lower mean body weight. Mortality occurred during early post-weaning period at 30 mg/kg/day (males only) and higher doses (both sexes) on PND 22, 23 or 24. Systemic exposures at the LOEL for these findings (30 mg/kg/day) in males and females were 11 times and 14 times the MRHD based upon total exposure.
The NOAEL for lurasidone hydrochloride neurobehavioral effect was 3 mg/kg/day in males and <3 mg/kg/day in females. Hyperactivity was noted during the post-treatment period starting at 30 mg/kg/day in males and 3 mg/kg/day in females (11 and 7 times the MRHD, respectively, based upon total exposure) and was still present at the end of the post-treatment period.
Histopathological findings included increased colloid in the thyroids and inflammation of the prostate in males at 150 mg/kg/day (22 times the MRHD based upon total exposure), and mammary gland hyperplasia, increased mucification of the vagina, and increased ovarian atretic follicles in females at doses as low as 3 mg/kg/day (7 times the MRHD based upon total exposure). Some of these findings were attributed to transiently elevated serum prolactin which was seen in both sexes at all doses. However, there were no deviations in reproductive parameters (fertility, conception indices, spermatogenesis, estrous cycle, gestation length, parturition, number of pups born) at any dose level.
The NOAEL for the offspring of the treated juvenile animals was 3 mg/kg/day based on the lower birth weights and body weights/body weight gains during the postnatal period for the offspring of the treated juvenile animals at 30 and 300 mg/kg/day.
Carcinogenicity
Lifetime carcinogenicity studies were conducted in ICR mice and Sprague-Dawley rats. Lurasidone was administered orally at doses of 30, 100, 300, or 650 (the high dose was reduced from 1200 in males) mg/kg/day to ICR mice and 3, 12, or 36 (high dose reduced from 50) mg/kg/day to Sprague-Dawley rats.
In the mouse study, there were increased incidences of malignant mammary gland tumors and pituitary gland adenomas in females at all doses; the lowest dose tested produced plasma levels (AUC) approximately equal to those in humans receiving the maximum recommended human dose (MRHD) of 160 mg/day. No increases in tumors were seen in male mice up to the highest dose tested, which produced plasma levels (AUC) 7 - 13 times those in humans receiving the MRHD.
In rats, an increased incidence of mammary gland carcinomas was seen in females at the two higher doses; the no-effect dose of 3 mg/kg produced plasma levels (AUC) 0.4 times those in humans receiving the MRHD. No increases in tumors were seen in male rats up to highest dose tested, which produced plasma levels (AUC) 6 times those in humans receiving the MRHD.
Mutagenesis
The potential for the genotoxicity of lurasidone has been adequately studied in varied test systems including in vitro assays in bacterial and mammalian cell systems (with and without metabolic activation) and in an in vivo micronucleus assay in mice. Lurasidone was shown not to be mutagenic or clastogenic under the conditions of these well-controlled assays.
Drug Dependence
The drug dependence studies in rats and monkeys did not indicate potential for lurasidone to induce psychic and physical dependence. Lurasidone was not self-administered by monkeys trained to self-administer barbiturate, did not suppress barbiturate withdrawal signs, and did not produce withdrawal signs after discontinuation of repeated dosing.
Antigenicity
Lurasidone caused delayed-type allergic reactions under strong sensitizing conditions in which it was subcutaneously administered at a dose 3 times the proposed clinical dose of 160 mg/day, along with Freund’s complete adjuvant. However, as lurasidone did not show antigenicity in active systemic anaphylactic reaction assays, passive cutaneous anaphylactic reaction assays, or gel precipitation reaction nor on intradermal tests when orally administered, it is unlikely that lurasidone will show antigenicity when orally administered to humans.
Phototoxicity
Oral administration of lurasidone to rats prior to irradiation with ultraviolet A (UVA) radiation at a dose of 10 J/cm2 produced no remarkable skin reaction or increase in ear thickness. It was concluded that lurasidone had no phototoxic effect on the skin under the conditions of the present study and is unlikely to show phototoxicity when orally administered to humans.
REFERENCES
DelBello M et al. Efficacy and Safety of Lurasidone in Children and Adolescents with Bipolar I Depression: A Double-Blind, Placebo-Controlled Study. J Am Acad Child Adolesc Psychiatry 2017;56(12):1015-1025.
Findling RL et al. Pharmacokinetics and Tolerability of Lurasidone in Children and Adolescents With Psychiatric Disorders. Clin Ther 2015;37(12):2788-2797.
Goldman R et al. Efficacy and Safety of Lurasidone in Adolescents with Schizophrenia: A 6-Week, Randomized Placebo-Controlled Study. J Child Adolesc Psychopharmacol 2017;27(6):516-525.
Loebel A et al. Efficacy and Safety of Lurasidone 80 mg/day and 160 mg/day in the Treatment of Schizophrenia: A Randomized, Double-Blind, Placebo- and Active-Controlled Trial. Schizophrenia Research 2013;145(1-3):101-109.
Loebel A et al. Lurasidone Monotherapy in the Treatment of Bipolar I Depression: A Randomized, Double-Blind, Placebo-Controlled Study. Am J Psychiatry 2014;171:160-168.
Loebel A et al. Lurasidone as Adjunctive Therapy with Lithium or Valproate for the Treatment of Bipolar I Depression: A Randomized, Double-Blind, Placebo-Controlled Study. Am J Psychiatry 2014;171:169-177.
Meltzer HY et al. Lurasidone in the Treatment of Schizophrenia: A Randomized, Double-Blind, Placebo- and Olanzapine-Controlled Study. Am J Psychiatry 2011;168:957–967.
Nasrallah HA et al. Lurasidone for the Treatment of Acutely Psychotic Patients with Schizophrenia: A 6-Week, Randomized, Placebo-Controlled Study. Journal of Psychiatric Research 2013;47:670-677.
Nakamura M et al. Lurasidone in the Treatment of Acute Schizophrenia: A Double-Blind, Placebo-Controlled Trial. J Clin Psychiatry. 2009;70(6):829-836.
Osaga M et al. Lurasidone in the Treatment of Schizophrenia: A 6-week, Placebo-Controlled Study. Psychopharmacology 2013;225:519–530.
Product Monograph, Latuda® (lurasidone hydrochloride tablets) by Sunovion Pharmaceuticals Canada Inc. Control No.: 234629. Date of Revision: March 18, 2020.