


Product Monograph - Teva-Finasteride
RECENT MAJOR LABEL CHANGES
7 WARNINGS AND PRECAUTIONS, Psychiatric 09/2025
TABLE OF CONTENTS
Sections or subsections that are not applicable at the time of authorization are not listed. RECENT MAJOR LABEL CHANGES ....................................................................................................... 2 TABLE OF CONTENTS ......................................................................................................................... 2 PART I: HEALTH PROFESSIONAL INFORMATION ................................................................................. 4 1 INDICATIONS ......................................................................................................................... 4
1.1 Pediatrics (<18 years of age) ..................................................................................................... 4 1.2 Geriatrics (>65 years of age) ..................................................................................................... 4 2 CONTRAINDICATIONS ............................................................................................................ 4 4 DOSAGE AND ADMINISTRATION ............................................................................................ 4
4.1 Dosing Considerations ......................................................................................................... 4 4.2 Recommended Dose and Dosage Adjustment ................................................................... 5 4.4 Administration ..................................................................................................................... 5 4.5 Missed Dose ........................................................................................................................ 5 5 OVERDOSAGE ........................................................................................................................ 5 6 DOSAGE FORMS, STRENGTHS, COMPOSITION AND PACKAGING ............................................. 6 7 WARNINGS AND PRECAUTIONS ............................................................................................. 6
7.1 Special Populations ............................................................................................................. 8 7.1.1 Pregnant Women ................................................................................................................ 8 7.1.2 Breast-feeding ..................................................................................................................... 8 7.1.3 Pediatrics (< 18 years of age) .............................................................................................. 8 7.1.4 Geriatrics ............................................................................................................................. 9 8 ADVERSE REACTIONS ............................................................................................................. 9
8.1 Adverse Reaction Overview ................................................................................................ 9 8.2 Clinical Trial Adverse Reactions ........................................................................................... 9 8.4 Abnormal Laboratory Findings .......................................................................................... 12 8.5 Post-Market Adverse Reactions ........................................................................................ 12 9 DRUG INTERACTIONS ........................................................................................................... 13
9.2 Drug Interactions Overview .............................................................................................. 13 9.4 Drug-Drug Interactions ...................................................................................................... 13 10 CLINICAL PHARMACOLOGY .................................................................................................. 13
10.1 Mechanism of Action ........................................................................................................ 13 10.2 Pharmacodynamics ........................................................................................................... 13 10.3 Pharmacokinetics .............................................................................................................. 15 11 STORAGE, STABILITY AND DISPOSAL .................................................................................... 17 12 SPECIAL HANDLING INSTRUCTIONS ...................................................................................... 17 PART II: SCIENTIFIC INFORMATION .................................................................................................. 18 13 PHARMACEUTICAL INFORMATION ....................................................................................... 18
TEVA-FINASTERIDE (Finasteride Tablets) Page 3 of 35 14 CLINICAL TRIALS................................................................................................................... 19
14.1 Clinical Trials by Indication ................................................................................................ 19 14.2 Comparative Bioavailability Studies ...................................................................................... 25 15 MICROBIOLOGY ................................................................................................................... 26 16 NON-CLINICAL TOXICOLOGY ................................................................................................ 26 17 SUPPORTING PRODUCT MONOGRAPHS ............................................................................... 30 PATIENT MEDICATION INFORMATION ............................................................................................. 31
TEVA-FINASTERIDE (Finasteride Tablets) Page 4 of 35
PART I: HEALTH PROFESSIONAL INFORMATION
1 INDICATIONS
TEVA-FINASTERIDE (finasteride) is a Type II 5 α-reductase inhibitor, indicated as monotherapy for the treatment and control of benign prostatic hyperplasia (BPH) and for the prevention of urologic events to:
- Reduce the risk of acute urinary retention;
Reduce the risk of surgery including transurethral resection of the prostate
(TURP) and prostatectomy.
- TEVA-FINASTERIDE causes regression of the enlarged prostate, improves urinary flow and improves the symptoms associated with BPH.
Limitations of Use
- TEVA-FINASTERIDE is not approved for the prevention of prostate cancer.
Patients with an enlarged prostate are the appropriate candidates for therapy with TEVA-FINASTERIDE.
1.1 Pediatrics (<18 years of age)
No data are available to Health Canada; therefore, Health Canada has not authorized an indication for pediatric use (see 14 CLINICAL TRIALS).
1.2 Geriatrics (>65 years of age)
Evidence from clinical studies and experience suggests that use in geriatric populations is associated with no significant differences in safety or effectiveness.
2 CONTRAINDICATIONS
TEVA-FINASTERIDE is contraindicated in the following:
Pregnant Women - Use in women when they are or may potentially be pregnant (see 7
WARNINGS AND PRECAUTIONS, 7.1 Special Populations, 7.1.1 Pregnant Women, Exposure to Finasteride - Risk to Male Fetus);
- Hypersensitivity to any component of this product.
TEVA-FINASTERIDE is not indicated for use in women or children.
4 DOSAGE AND ADMINISTRATION
4.1 Dosing Considerations
TEVA-FINASTERIDE (Finasteride Tablets) Page 5 of 35
TEVA-FINASTERIDE (finasteride tablets) as monotherapy is indicated for the treatment and control of benign prostatic hyperplasia (BPH) and for the prevention of urologic events to:
- Reduce the risk of acute urinary retention;
Reduce the risk of surgery including transurethral resection of the prostate
(TURP) and prostatectomy.
- TEVA-FINASTERIDE causes regression of the enlarged prostate, improves urinary flow and improves the symptoms associated with BPH.
4.2 Recommended Dose and Dosage Adjustment
The recommended dosage of TEVA-FINASTERIDE is one 5 mg tablet daily with or without food (see 14 CLINICAL TRIALS).
Dosage in Renal Insufficiency: No adjustment in dosage is required in patients with varying degrees of renal insufficiency (creatinine clearances as low as 0.15 mL/s [9 mL/min]) as pharmacokinetic studies did not indicate any change in the disposition of finasteride.
Dosage in Geriatrics: No adjustment in dosage is required although pharmacokinetic studies indicated the elimination of finasteride is decreased in patients more than 70 years of age (see 10 CLINICAL PHARMACOLOGY, 10.3 Pharmacokinetics).
4.4 Administration
TEVA-FINASTERIDE is for oral administration.
4.5 Missed Dose
If a tablet is missed at its usual time, an extra dose should not be taken. The next dose should be taken as usual.
5 OVERDOSAGE
Patients have received single doses of finasteride up to 400 mg and multiple doses of finasteride up to 80 mg/day for three months without adverse reactions.
For the most recent information in the management of a suspected drug overdose, contact your regional poison control centre or Health Canada's toll-free number, 1-844 POISON-X (1-844-764-7669).
TEVA-FINASTERIDE (Finasteride Tablets) Page 6 of 35
6 DOSAGE FORMS, STRENGTHS, COMPOSITION AND PACKAGING
Table 1 – Dosage Forms, Strengths, Composition and Packaging
Route of Administration | Dosage Form / Strength / Composition | Non-Medicinal Ingredients |
| Oral | Film-coated Tablets 5 mg | lactose monohydrate, magnesium stearate, microcrystalline cellulose, opadry blue (hypromellose, polyethylene glycol, titanium dioxide, FD&C Blue #2 Indigo Carmine Aluminum Lake 11%-14%), povidone, pregelatinized starch, sodium lauryl sulfate and sodium starch glycolate |
TEVA-FINASTERIDE 5 mg tablets are blue, round biconvex film-coated tablets, engraved with FT5 on one side and plain on the other. Available in blister packages of 30 tablets and bottle of 30 and 100 tablets.
7 WARNINGS AND PRECAUTIONS
General
Patients with large residual urine volume and/or severely diminished urinary flow should be carefully monitored for obstructive uropathy.
TEVA-FINASTERIDE is not indicated for those patients who are candidates for immediate surgery.
No studies have been conducted to determine if finasteride can be used for the control of prostatic hyperplasia in asymptomatic patients.
The long term (>10 years) beneficial and adverse effects of finasteride have not yet been established.
Prior to treatment with TEVA-FINASTERIDE, the patient should undergo a thorough urological evaluation to determine the severity of the condition, and to exclude the need for immediate surgery or the possibility of carcinoma of the prostate. Periodic follow-up evaluations should be performed to determine whether a clinical response has occurred.
Physicians should instruct their patients to promptly report any changes in their breasts such as lumps, pain or nipple discharge. Breast changes including breast enlargement, tenderness and neoplasm have been reported (see 8 ADVERSE REACTIONS).
TEVA-FINASTERIDE (Finasteride Tablets) Page 7 of 35
Carcinogenesis and Mutagenesis
Increased Risk of High-Grade Prostate Cancer
Men aged 55 and over with a normal digital rectal examination and PSA ≤3.0 ng/mL at baseline taking finasteride 5 mg/day in the 7-year Prostate Cancer Prevention Trial (PCPT) had an increased risk of Gleason score 8-10 prostate cancer (finasteride 1.8% vs placebo 1.1%) (See 1 INDICATIONS and 8 ADVERSE REACTIONS). Similar results were observed in a 4-year placebo-controlled clinical trial with another 5α-reductase inhibitor (dutasteride) (1% dutasteride vs 0.5% placebo). 5α-reductase inhibitors may increase the risk of development of high-grade prostate cancer. Whether the effect of 5α-reductase inhibitors to reduce prostate volume, or study-related factors, impacted the results of these studies has not been established.
Prior to initiating therapy with TEVA-FINASTERIDE, appropriate evaluation should be conducted to rule out other urological conditions, including prostate cancer that might mimic BPH.
Monitoring and Laboratory Tests
Effects on PSA and Prostate Cancer Detection
In clinical studies, finasteride reduced serum PSA concentration by approximately 50% within six months of treatment. This decrease is predictable over the entire range of PSA values in patients with symptomatic BPH, although it may vary in individuals.
For interpretation of serial PSAs in men taking TEVA-FINASTERIDE, a new PSA baseline should be established at least six months after starting treatment and PSA monitored periodically thereafter. Any confirmed increase from the lowest PSA value while on TEVA-FINASTERIDE may signal the presence of prostate cancer and should be evaluated, even if PSA levels are still within the normal range for men not taking a 5α-reductase inhibitor. Non-compliance with finasteride therapy may also affect PSA test results. To interpret an isolated PSA value in patients treated with TEVA-FINASTERIDE for six months or more, PSA values should be doubled for comparison with normal ranges in untreated men. These adjustments preserve the utility of PSA to detect prostate cancer in men treated with TEVA-FINASTERIDE.
TEVA-FINASTERIDE may also cause decreases in serum PSA in the presence of prostate cancer. The ratio of free to total PSA (percent free PSA) remains constant even under the influence of finasteride. If clinicians elect to use percent free PSA as an aid in the detection of prostate cancer in men undergoing finasteride therapy, no adjustment to its value appears necessary.
Effect on Levels of PSA
Serum PSA concentration is correlated with patient age and prostatic volume, and prostatic volume is correlated with patient age. When PSA laboratory determinations are evaluated, consideration should be given to the fact that PSA levels decrease in patients treated with TEVA-FINASTERIDE.
TEVA-FINASTERIDE (Finasteride Tablets) Page 8 of 35
Psychiatric
There have been post-marketing reports of serious psychiatric symptoms in patients being treated with finasteride that sometimes continued after treatment discontinuation. Mood alterations including depressed mood, depression, self-harm injury, suicidal ideation, as well as worsening of pre-existing depression (psychiatric disorder) have been reported in patients treated with finasteride (see 8 ADVERSE REACTIONS, 8.3 Post-Market Adverse Reactions). It is recommended that all patients be screened for suicidal ideation, self-harm, and depression and/or associated risk factors before treatment initiation.
Clinical monitoring of all patients for signs and symptoms of psychiatric disorder should continue throughout treatment and after. If these occur, patients should be advised to seek medical advice, as soon as possible.
7.1 Special Populations
7.1.1 Pregnant Women
TEVA-FINASTERIDE is contraindicated for use in women when they are or may potentially be pregnant (see 2 CONTRAINDICATIONS). Because of the ability of Type II 5 alpha-reductase inhibitors such as finasteride to inhibit conversion of testosterone to dihydrotestosterone, TEVA-FINASTERIDE may cause abnormalities of the external genitalia of a male fetus when administered to a pregnant woman. In female rats, low doses of finasteride administered during pregnancy have produced abnormalities of the external genitalia in male offspring. Therefore, if this drug is used during pregnancy or if pregnancy occurs while taking or exposed to this drug, the pregnant woman should be apprised of the potential hazard to the male fetus (see 16 NON-CLINICAL TOXICOLOGY, Reproductive and Developmental Toxicology).
Exposure to Finasteride – Risk to Male Fetus:
Women should not handle crushed or broken tablets of TEVA-FINASTERIDE when they are or may potentially be pregnant because of the possibility of absorption of finasteride and the subsequent potential risk to a male fetus (see 7 WARNINGS AND PRECAUTIONS, 7.1 Special Populations, 7.1.2 Breast-feeding). TEVA-FINASTERIDE tablets are coated and will prevent contact with the active ingredient during normal handling, provided that the tablets have not been broken or crushed.
7.1.2 Breast-feeding
It is not known whether finasteride is excreted in human milk.
7.1.3 Pediatrics (< 18 years of age)
No data are available to Health Canada; therefore, Health Canada has not authorized an TEVA-FINASTERIDE (Finasteride Tablets) Page 9 of 35 indication for pediatric use (see 14 CLINICAL TRIALS). Safety and effectiveness in children have not been established.
7.1.4 Geriatrics
Evidence from clinical studies and experience suggests that use in geriatric populations is associated with no significant differences in safety or effectiveness.
8 ADVERSE REACTIONS
8.1 Adverse Reaction Overview
The following clinically significant adverse effects may be associated with the treatment of TEVA-FINASTERIDE (see 7 WARNINGS AND PRECAUTIONS):
- Male breast cancer
- High-grade prostate cancer
- Mood disorders such as depression, self-harm injury, suicidal ideation, worsening of preexisting depression
- Abnormalities of male fetus
8.2 Clinical Trial Adverse Reactions
Clinical trials are conducted under very specific conditions. The adverse reaction rates observed in the clinical trials; therefore, may not reflect the rates observed in practice and should not be compared to the rates in the clinical trials of another drug. Adverse reaction information from clinical trials may be useful in identifying and approximating rates of adverse drug reactions in real-world use.
In PLESS, 1524 patients treated with finasteride 5 mg daily and 1516 patients treated with placebo were evaluated for safety over a period of 4 years. 4.9% (74 patients) were discontinued from treatment due to side effects associated with finasteride compared with 3.3% (50 patients) treated with placebo. 3.7% (57 patients) treated with finasteride and 2.1% (32 patients) treated with placebo discontinued therapy as a result of side effects related to sexual function, which were the most frequently reported side effects.
Table 2 presents the only clinical adverse reactions considered possibly, probably or definitely drug related by the investigator, for which the incidence on finasteride was ≥ 1% and greater than placebo over the 4 years of the study. In years 2-4 of the study, there was no significant difference between treatment groups in the incidences of impotence, decreased libido, and ejaculation disorder.
TEVA-FINASTERIDE (Finasteride Tablets) Page 10 of 35
Table 2 Drug-Related Adverse Reactions
| Treatment | Year 1 (%) | Years 2, 3 and 4* (%) | |
| Impotence | Placebo Finasteride | 3.7 8.1 | 5.1 5.1 |
| Decreased Libido | Placebo Finasteride | 3.4 6.4 | 2.6 2.6 |
| Decreased Volume of Ejaculate | Placebo Finasteride | 0.8 3.7 | 0.5 1.5 |
| Ejaculation Disorder | Placebo Finasteride | 0.1 0.8 | 0.1 0.2 |
| Breast Enlargement | Placebo Finasteride | 0.1 0.5 | 1.1 1.8 |
| Breast Tenderness | Placebo Finasteride | 0.1 0.4 | 0.3 0.7 |
| Rash | Placebo Finasteride | 0.2 0.5 | 0.1 0.5 |
* Combined years 2-4
The adverse reaction profile in the one-year, placebo-controlled, Phase III studies and the five-year extensions, including 853 patients treated for 5 to 6 years, was similar to that reported in years 2-4 in PLESS. There is no evidence of increased adverse reactions with increased duration of treatment with finasteride. The incidence of new drug related sexual adverse reactions decreased with duration of treatment.
Medical Therapy of Prostatic Symptoms (MTOPS)
The MTOPS study compared finasteride 5 mg/day (n=768), doxazosin 4 or 8 mg/day (n=756), combination therapy of finasteride 5 mg/day and doxazosin 4 or 8 mg/day (n=786), and placebo (n=737). In this study, the safety and tolerability profile of the combination therapy was generally consistent with the profiles of the individual components. The incidence of ejaculation disorder in patients receiving combination therapy was comparable to the sum of incidences of this adverse reaction for the two monotherapies. The individual adverse effects that occurred more frequently in the combination group compared to either drug alone were: asthenia, postural hypotension, peripheral edema, dizziness, decreased libido, rhinitis, abnormal ejaculation, impotence and abnormal sexual function (see Table 3).
Four patients in MTOPS reported the adverse reaction breast cancer. Three of these patients were on finasteride only and one was on the combination therapy. During the four year, placebo-controlled PLESS study, which enrolled 3040 men, there were 2 cases of breast cancer in the placebo treated men, but no cases were reported in men treated with finasteride. The relationship between the long-term use of finasteride and male breast cancer is currently unknown.
TEVA-FINASTERIDE (Finasteride Tablets) Page 11 of 35
Table 3 Drug-Related Clinical Adverse Reactions in MTOPS
Incidence ≥ 2% in One or More Treatment Groups
Adverse Reactions
Placebo (N=737) (%) | Doxazosin 4 mg or 8 mg* (N=756) (%) | Finasteride (N=768) (%) | Combination (N=768) (%) | |
| Body as a whole | ||||
| Asthenia Headache | 7.1 2.3 | 15.7 4.1 | 5.3 2.0 | 16.8 2.3 |
| Cardiovascular | ||||
Hypotension Postural Hypotension | 0.7 8.0 | 3.4 16.7 | 1.2 9.1 | 1.5 17.8 |
| Metabolic and Nutritional | ||||
| Peripheral Edema | 0.9 | 2.6 | 1.3 | 3.3 |
| Nervous | ||||
Dizziness Libido Decreased Somnolence | 8.1 5.7 1.5 | 17.7 7.0 3.7 | 7.4 10.0 1.7 | 23.2 11.6 3.1 |
| Respiratory | ||||
| Dyspnea Rhinitis | 0.7 0.5 | 2.1 1.3 | 0.7 1.0 | 1.9 2.4 |
| Urogenital | ||||
Abnormal Ejaculation Gynecomastia Impotence Sexual Function Abnormal | 2.3 0.7 12.2 0.9 | 4.5 1.1 14.4 2.0 | 7.2 2.2 18.5 2.5 | 14.1 1.5 22.6 3.1 |
*Doxazosin dose was achieved by weekly titration (1 to 2 to 4 to 8 mg). The final tolerated dose (4 mg or 8 mg) was administered at end-Week 4. Only those patients tolerating at least 4 mg were kept on doxazosin. The majority of patients received the 8-mg dose over the duration of the study.
Other Long Term Data
High-Grade Prostate Cancer
The PCPT trial was a 7-year randomized, double-blind, placebo-controlled trial that enrolled 18,882 men ≥55 years of age with a normal digital rectal examination and a PSA ≤ 3.0 ng/mL. Men received either finasteride 5 mg or placebo daily. Patients were evaluated annually with PSA and digital rectal exams. Biopsies were performed for elevated PSA, an abnormal digital rectal exam, or the end of study. The incidence of Gleason score 8-10 prostate cancer was higher in men treated with finasteride (1.8%) than in those treated with placebo (1.1%) [See 1 INDICATIONS and 7 WARNINGS AND PRECAUTIONS]. In a 4-year placebo controlled clinical trial with another 5α-reductase inhibitor (dutasteride), similar results for Gleason score 8-10 prostate cancer were observed (1% dutasteride vs 0.5% placebo).
TEVA-FINASTERIDE (Finasteride Tablets) Page 12 of 35
No clinical benefit has been demonstrated in patients with prostate cancer treated with finasteride.
8.4 Abnormal Laboratory Findings
Laboratory Tests
When PSA laboratory determinations are evaluated, consideration should be given to the fact that PSA levels are decreased in patients treated with TEVA-FINASTERIDE (see 7 WARNINGS AND PRECAUTIONS, Monitoring and Laboratory Tests, Effects on PSA and Prostate Cancer Detection).
In most patients, a rapid decrease in PSA is seen within the first months of therapy, after which time PSA levels stabilize to a new baseline. The post-treatment baseline approximates half of the pre-treatment value. Therefore, in typical patients treated with TEVA-FINASTERIDE for six months or more, PSA values should be doubled for comparison to normal ranges in untreated men. For clinical interpretation, see 7 WARNINGS AND PRECAUTIONS, Monitoring and Laboratory Tests, Effects on PSA and Prostate Cancer Detection.
No other difference in standard laboratory parameters was observed between patients treated with placebo or finasteride.
8.5 Post-Market Adverse Reactions
The following additional adverse reactions have been reported in post-marketing surveillance system with finasteride and/or finasteride at lower doses. Because these reactions are reported voluntarily from a population of uncertain size, it is not always possible to reliably estimate the frequency or establish a causal relationship to drug exposure.
Immune system disorders: hypersensitivity reactions, such as pruritus, urticaria and angioedema (including swelling of the lips, tongue, throat and face);
Musculoskeletal and connective tissue disorders: Rare cases of the following have been reported: rhabdomyolysis, myopathy, myalgia, myasthenia, and CK elevation. In some cases, these events were found to be reversible with discontinuation of finasteride therapy.
Psychiatric disorders: mood alterations and depression, decreased libido that continued after discontinuation of treatment. Mood alterations including depressed mood and, less frequently, suicidal ideation have been reported in patients treated with finasteride 5 mg. Patients should be monitored for psychiatric symptoms and if these occur, the patient should be advised to seek medical advice.
Reproductive system and breast disorders: sexual dysfunction (erectile dysfunction and ejaculation disorders) that continued after discontinuation of treatment, male TEVA-FINASTERIDE (Finasteride Tablets) Page 13 of 35
breast cancer, testicular pain, hematospermia, male infertility and/or poor seminal quality. Normalization or improvement of seminal quality has been reported after discontinuation of finasteride.
9 DRUG INTERACTIONS
9.2 Drug Interactions Overview
No drug interactions of clinical importance have been identified. Finasteride at prescribed doses, does not appear to affect significantly the cytochrome P450-linked drug metabolizing enzyme system. Compounds which have been tested in man have included propranolol, digoxin, glyburide, warfarin, theophylline and antipyrine and no clinically meaningful interactions were found. However, patients on medications with narrow therapeutic indices, such as phenytoin, should be carefully monitored when treatment with TEVA-FINASTERIDE is initiated.
9.4 Drug-Drug Interactions
Although specific interaction studies were not performed, in clinical studies finasteride was used concomitantly with ACE-inhibitors, acetaminophen, acetylsalicylic acid, alpha-blockers, beta-blockers, calcium channel blockers, cardiac nitrates, diuretics, H2 antagonists, HMG-CoA reductase inhibitors, nonsteroidal anti-inflammatory drugs (NSAIDs), quinolones and benzodiazepines without evidence of clinically significant adverse interactions.
10 CLINICAL PHARMACOLOGY
10.1 Mechanism of Action
Finasteride a synthetic 4-azasteroid compound, is an inhibitor of Type II 5 alpha-reductase, an intracellular enzyme which metabolizes testosterone into the more potent androgen dihydrotestosterone (DHT). In benign prostatic hyperplasia (BPH), enlargement of the prostate gland is dependent upon the conversion of testosterone to DHT within the prostate. Finasteride is highly effective in reducing circulating and intraprostatic DHT. Finasteride has very low affinity for the androgen receptor.
In the finasteride Long-Term Efficacy and Safety Study (PLESS), the effect of therapy with finasteride on BPH-related urologic events (surgical intervention [e.g., transurethral resection of the prostate and prostatectomy] or acute urinary retention requiring catheterization) was assessed over a 4-year period in 3016 patients with moderate to severe symptoms of BPH. In this double-blind, randomized, placebo-controlled multicenter study, treatment with finasteride reduced the risk of total urologic events by 51% and was also associated with a marked and sustained regression in prostate volume, and a sustained increase in maximum urinary flow rate and improvement in symptoms.
10.2 Pharmacodynamics
Benign prostatic hyperplasia (BPH) occurs in the majority of men over the age of 50 and its prevalence increases with age. Epidemiologic studies suggest that enlargement of the prostate TEVA-FINASTERIDE (Finasteride Tablets) Page 14 of 35 gland is associated with a 3-fold increase in the risk of acute urinary retention and prostate surgery. Men with enlarged prostates are also 3 times more likely to have moderate to severe urinary symptoms or a decrease in urinary flow than men with smaller prostates.
The development and enlargement of the prostate gland and subsequent BPH are dependent upon the potent androgen, dihydrotestosterone (DHT). Testosterone, secreted by the testes and adrenal glands, is rapidly converted to DHT by Type II 5α-reductase predominantly in the prostate gland, epididymis, liver, and skin where it is then preferentially bound to the cell nucleus in those tissues.
Finasteride is a competitive inhibitor of human Type II 5α-reductase with which it slowly forms a stable enzyme complex. Turnover from this complex is extremely slow (t½ ~30 days). In vitro and in vivo, finasteride has been demonstrated to be a specific Type II 5α-reductase inhibitor, and has very low affinity for the androgen receptor.
A single 5 mg dose of finasteride produced a rapid reduction in the serum concentration of DHT, with the maximum effect observed after 8 hours. While plasma levels of finasteride varied over 24 hours, serum DHT levels remained constant during this period indicating that plasma concentrations of drug do not directly correlate with the plasma concentrations of DHT. In patients with BPH, finasteride, given for four years at a dose of 5 mg/day was shown to reduce circulating DHT concentrations by approximately 70% and was associated with a median reduction in prostate volume of approximately 20%. Additionally, PSA was reduced approximately 50% from baseline values, suggesting a reduction in prostate epithelial cell growth. Suppression of DHT levels and regression of the hyperplastic prostate with the associated decrease in PSA levels have been maintained in studies of up to four years. In these studies, circulating levels of testosterone were increased by approximately 10-20% yet remained within the physiologic range.
When finasteride was given for 7-10 days to patients scheduled for prostatectomy, the drug caused a decrease in intraprostatic DHT of approximately 80%. Intraprostatic concentrations of testosterone were increased up to 10 times over pre-treatment levels.
In healthy volunteers treated with finasteride for 14 days, discontinuation of therapy resulted in a return of DHT values to pretreatment levels within approximately 2 weeks. In patients treated for three months, prostate volume, which declined by approximately 20% returned to close to baseline value after approximately three months of discontinuation of therapy.
Finasteride had no effect compared to placebo on circulating levels of cortisol, estradiol, prolactin, thyroid-stimulating hormone, or thyroxine. No clinically meaningful effect was observed on the plasma lipid profile (i.e. total cholesterol, low density lipoproteins, high density lipoproteins and triglycerides) or bone mineral density. An increase of approximately 15% in luteinizing hormone (LH) and 9% in follicle-stimulating hormone (FSH) was observed in patients treated for 12 months; however, these levels remained well within the physiologic range. Gonadotropin-releasing hormone (GnRH) stimulated levels of LH and FSH were not altered, indicating that regulatory control of pituitary-testicular axis was not affected. Treatment with finasteride for 24 weeks to evaluate semen parameters in healthy male volunteers revealed no TEVA-FINASTERIDE (Finasteride Tablets) Page 15 of 35 clinically meaningful effects on sperm concentration motility, morphology or pH. A 0.6 mL median decrease in ejaculate volume with a concomitant reduction in total sperm per ejaculate was observed. These parameters remained within the normal range and were reversible upon discontinuation of therapy.
Finasteride appeared to inhibit both C19 and C21 steroid metabolism and hence appeared to have an inhibitory effect on both hepatic and peripheral Type II 5α-reductase activity. The serum DHT metabolites androstenediol glucuronide and androsterone glucuronide were also significantly reduced. This metabolic pattern is similar to that observed in individuals with a genetic deficiency of Type II 5α-reductase who have markedly decreased levels of DHT and small prostates, and who do not develop BPH. These individuals have urogenital defects at birth and biochemical abnormalities but have no other clinically important disorders as a consequence of Type II 5 α-reductase deficiency.
10.3 Pharmacokinetics
In a study in 15 healthy male subjects, the mean bioavailability of a 5 mg finasteride tablet was 63% (range, 34-108%), based on the ratio of the area under the curve (AUC) relative to a 5 mg intravenous dose infused over 60 minutes. Following the intravenous infusion, mean plasma clearance was 2.75 mL/s (range, 1.17 - 4.65 mL/s) (165 mL/min, range, 70-279 mL/min) and mean steady-state volume of distribution was 76 liters (range, 44-96 liters). In a separate study, the bioavailability of finasteride was not affected by food.
In two studies of healthy subjects (n=69) receiving finasteride 5 mg/day for 6-24 weeks, finasteride concentrations in semen ranged from undetectable (<0.1 ng/mL) to 10.54 ng/mL. In an earlier study using a less sensitive assay, finasteride concentrations in the semen of 16 subjects receiving finasteride 5 mg/day ranged from undetectable (<1.0 ng/mL) to 21 ng/mL. Thus, based on a 5 mL ejaculate volume, the amount of finasteride in ejaculate was estimated 50- to 100-fold less than the dose of finasteride (5 micrograms) that had no effect on circulating DHT levels in adult males (see 16 NON-CLINICAL TOXICOLOGY, Reproductive and Developmental Toxicology).
Finasteride has been recovered in the cerebrospinal fluid (CSF) of patients treated with a 7-10 day course of finasteride, but the drug does not appear to concentrate preferentially to the CSF.
Absorption:
Maximum finasteride plasma concentration averaged 37 ng/mL (range, 27-49 ng/mL) and was reached 1 to 2 hours post dose. The mean plasma half-life of elimination was 6 hours (range, 3- 16 hours).
Distribution:
There is a slow accumulation phase for finasteride after multiple dosing. After dosing with 5 mg/day of finasteride for 17 days, plasma concentrations of finasteride were 47% and 54% higher than after the first dose in men 45-60 years old (n=12) and ≥70 years old (n=12), TEVA-FINASTERIDE (Finasteride Tablets) Page 16 of 35 respectively. Mean trough concentrations after 17 days of dosing were 6.2 ng/mL (range, 2.4- 9.8 ng/mL) and 8.1 ng/mL (range, 1.8-19.7 ng/mL), respectively in the two age groups. Although steady state was not reached in this study, mean trough plasma concentration in another study in patients with BPH (mean age, 65 years) receiving 5 mg/day was 9.4 ng/mL (range, 7.1-13.3 ng/mL; n=22) after over a year of dosing.
Finasteride has been recovered in the cerebrospinal fluid (CSF) of patients treated with a 7-10 day course of finasteride, but the drug does not appear to concentrate preferentially to the CSF.
Metabolism:
Following an oral dose of 14C-finasteride in man, a mean of 39% (range, 32-46%) of the dose was excreted in the urine in the form of metabolites; and 57% (range, 51-64%) was excreted in the feces. The major compound isolated from urine was the monocarboxylic acid metabolite; virtually no unchanged drug was recovered. The t-butyl side chain monohydroxylated metabolite has been isolated from plasma. These metabolites possess no more than 20% of the 5α-reductase inhibitory activity of finasteride.
Elimination:
The elimination rate of finasteride is decreased in the elderly, but no dosage adjustment is necessary. The mean terminal half-life of finasteride in subjects ≥70 years of age was approximately 8 hours (range, 6-15 hours) compared to 6 hours (range, 4-12 hours) in subjects 45-60 years of age. As a result, mean area under the curve [AUC] (0-24 hr) after 17 days of dosing was 15% higher in subjects ≥70 years of age (p=0.02).
Special Populations and Conditions
- Renal Insufficiency
No dosage adjustment is necessary in patients with renal insufficiency. In patients with chronic renal impairment, with creatinine clearances ranging from 0.15 to 0.92 mL/s (9.0 to 55 mL/min), AUC, maximum plasma concentration, half-life, and protein binding after a single dose of 14C - finasteride were similar to values obtained in healthy volunteers. Urinary excretion of metabolites was decreased in patients with renal impairment. This decrease was associated with an increase in fecal excretion of metabolites. Plasma concentrations of metabolites were significantly higher in patients with renal impairment (based on a 60% increase in total radioactivity AUC). However, finasteride has been well tolerated in BPH patients with normal renal function receiving up to 80 mg/day for 12 weeks where exposure of these patients to metabolites would presumably be much greater.
- Geriatrics
No dosage adjustment is necessary for the elderly.
TEVA-FINASTERIDE (Finasteride Tablets) Page 17 of 35
11 STORAGE, STABILITY AND DISPOSAL
Store at room temperature between 15°C - 30°C and protect from light.
12 SPECIAL HANDLING INSTRUCTIONS
Women should not handle crushed or broken tablets of TEVA-FINASTERIDE when they are or may potentially be pregnant (see 7 WARNINGS AND PRECAUTIONS, 7.1 Special Populations, 7.1.1 Pregnant Women, Exposure to Finasteride - Risk to Male Fetus).
 TEVA-FINASTERIDE (Finasteride Tablets) Page 18 of 35 PART II: SCIENTIFIC INFORMATION
13 PHARMACEUTICAL INFORMATION
Drug Substance
Proper name: Finasteride
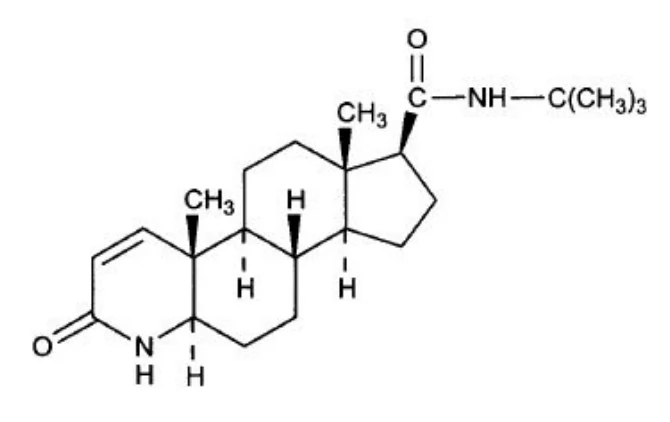
Chemical name: N-(1, 1-Dimethylethyl)-3-oxo-4-aza-5α-androst-1-ene-17β-carboxamide.
Molecular formula and molecular mass: C23H36N2O2; 372.54 g/mol
Structural formula:
Physicochemical properties: Finasteride is white or almost white, crystalline powder with a melting point of approximately 257°C. Finasteride is practically insoluble in water, freely soluble in ethanol and in methylene chloride.
TEVA-FINASTERIDE (Finasteride Tablets) Page 19 of 35 14 CLINICAL TRIALS
14.1 Clinical Trials by Indication
Treatment and control of benign prostatic hyperplasia (BPH) and prevention of urologic events
The data from the studies described below, showing reduced risk of acute urinary retention and surgery, improvement in BPH-related symptoms, increased maximum urinary flow rates, and decreasing prostate volume, suggest that finasteride reverses the progression of BPH in men with an enlarged prostate.
Finasteride 5 mg/day was initially evaluated in patients with symptoms of BPH and enlarged prostates by digital rectal examination in two 1-year, placebo-controlled, randomized, double-blind, Phase III studies and their 5-year open extensions. Of 536 patients originally randomized to receive finasteride 5 mg/day, 234 completed an additional 5 years of therapy and were available for analysis. The efficacy parameters were symptom score, maximum urinary flow rate, and prostate volume.
Finasteride was further evaluated in the finasteride Long-Term Efficacy and Safety Study (PLESS), a double-blind, randomized, placebo-controlled, 4-year multicenter study. In this study, the effect of therapy with finasteride 5 mg/day on symptoms of BPH and BPH-related urologic events (surgical intervention [e.g., transurethral resection of the prostate and prostatectomy] or acute urinary retention requiring catheterization) was assessed. 3040 patients between the ages of 45 and 78, with moderate to severe symptoms of BPH and an enlarged prostate upon digital rectal examination, were randomized into the study (1524 to finasteride, 1516 to placebo) and 3016 patients were evaluable for efficacy. 1883 patients completed the 4-year study (1000 in the finasteride group, 883 in the placebo group). Maximum urinary flow rate and prostate volume were also evaluated (see below for discussion of efficacy). Investigators collected adverse reaction information reported by patients during each visit to the clinic and were asked to assess drug relationship. The drug-related adverse reactions seen in PLESS were consistent with those seen in previous studies and are presented in the 8 ADVERSE REACTIONS section. Although the clinical significance is unclear, a higher incidence of cataracts (4.2%, finasteride vs. 2.5%, placebo) and diabetes (2.8%, finasteride vs. 1.7%, placebo) was observed in patients receiving finasteride. None of these cases were considered drug related by the investigator.
Effect on Acute Urinary Retention and the Need for Surgery
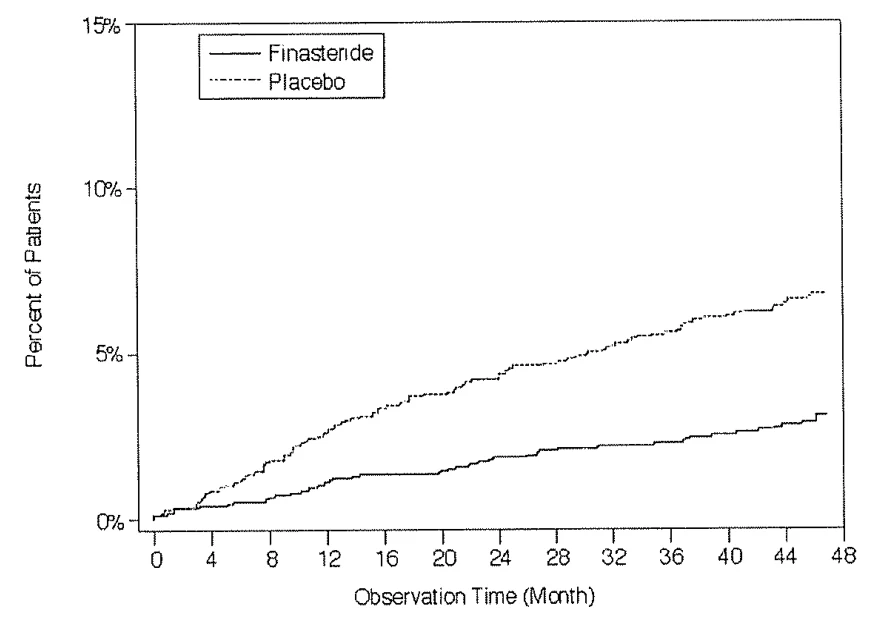
In the 4-year PLESS study, surgery or acute urinary retention requiring catheterization occurred in 13.2% of the patients taking placebo compared with 6.6% of the patients taking finasteride, representing a 51% reduction in risk for surgery or acute urinary retention over 4 years. Finasteride reduced the risk of surgery by 55% (10.1% for placebo vs. 4.6% for finasteride) and reduced the risk of acute urinary retention by 57% (6.6% for placebo vs. 2.8% for finasteride). The reduction in risk was evident between treatment groups at first evaluation (4 months) and was maintained throughout the 4-year study (see Figures 1 and 2). Table 4 below shows the rates of occurrence and risk reduction of urologic events during the study. 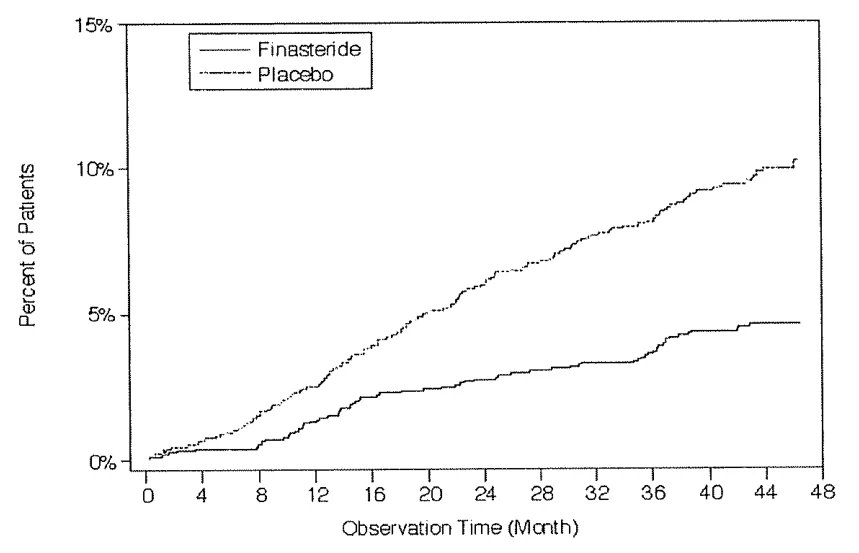
 TEVA-FINASTERIDE (Finasteride Tablets) Page 20 of 35
Figure 1 Percent of Patients Having Surgery for BPH, Including TURP
Figure 2 Percent of Patients Developing Acute Urinary Retention
(Spontaneous and Precipitated)
TEVA-FINASTERIDE (Finasteride Tablets) Page 21 of 35 Table 4 Rates of Urologic Events and Risk Reduction by Finasteride over 4 Years
| Urologic Events | Percent of Patients | Risk Reduction | |
| Placebo (n = 1503) | Finasteride 5 mg (n = 1513) | ||
| Surgery or Acute Urinary Retention | 13.2% | 6.6% | 51%* |
| Surgery† TURP | 10.1% 8.3% | 4.6% 4.2% | 55%* 49%* |
| Acute Urinary Retention | 6.6% | 2.8% | 57%* |
† BPH-related surgery
* p<0.001
Effect on Symptom Score
In the two 1-year, Phase III studies, mean total symptom scores decreased from baseline as early as week 2. Compared with placebo, a significant improvement in symptoms was observed by months 7 and 10 in these studies. Although an early improvement in urinary symptoms was seen in some patients, a therapeutic trial of at least 6 months was generally necessary to assess whether a beneficial response in symptom relief had been achieved. The improvement in BPH symptoms was maintained through the first year and throughout an additional 5 years of extension studies.
Patients in the 4-year PLESS study had moderate to severe symptoms at baseline (mean of approximately 15 points on a 0-34 point scale). In the patients who remained on therapy for the duration of the 4-year study, finasteride improved the symptom score by 3.3 points compared with 1.3 points in the placebo group (p<0.001). An improvement in symptom score was evident at 1 year in patients treated with finasteride, and this improvement continued through year 4. Symptom scores improved in patients treated with placebo in the first year but worsened thereafter. Patients with moderate to severe symptoms at baseline tended to have the greatest improvement in symptom score.
Effect on Maximum Urinary Flow Rate
In the two 1-year, Phase III studies, maximum urinary flow rate was significantly increased compared with baseline by week 2. Compared with placebo, a significant increase in maximum urinary flow rate was observed by months 4 and 7 in these studies. This effect was maintained through the first year and throughout an additional 5 years of extension studies.
In the 4-year PLESS study, there was a clear separation between treatment groups in maximum urinary flow rate in favor of finasteride by month 4, which was maintained throughout the study. Mean maximum urinary flow rate at baseline was approximately 11 mL/sec in both treatment groups. In the patients who remained on therapy for the duration of the study and had evaluable urinary flow data, finasteride increased maximum urinary flow rate by 1.9 mL/sec compared with 0.2 mL/sec in the placebo group.
TEVA-FINASTERIDE (Finasteride Tablets) Page 22 of 35 Effect on Prostate Volume
In the two 1-year, Phase III studies, mean prostate volume at baseline ranged between 40-50 cc. In both studies, prostate volume was significantly reduced compared with baseline and placebo at first evaluation (3 months). This effect was maintained through the first year and throughout an additional 5 years of extension studies.
In the 4-year PLESS study, prostate volume was assessed yearly by magnetic resonance imaging (MRI) in a subset of patients (n=284). In patients treated with finasteride, prostate volume was reduced compared with both baseline and placebo throughout the 4-year study. Of the patients in the MRI subset who remained on therapy for the duration of the study, finasteride decreased prostate volume by 17.9% (from 55.9 cc at baseline to 45.8 cc at 4 years) compared with an increase of 14.1% (from 51.3 cc to 58.5 cc) in the placebo group (p<0.001).
Prostate Volume as a Predictor of Therapeutic Response
A meta-analysis combining 1-year data from seven double-blind, placebo-controlled studies of similar design, including 4491 patients with symptomatic BPH, demonstrated that, in patients treated with finasteride, the magnitude of symptom response and degree of improvement in maximum urinary flow rate were greater in patients with an enlarged prostate (approximately 40 cc and greater) at baseline.
Medical Therapy of Prostatic Symptoms
The Medical Therapy of Prostatic Symptoms (MTOPS) Trial was a double-blind, randomized, placebo-controlled, multicenter, 4- to 6- year study (average 5 years) in 3047 men with symptomatic BPH, who were randomized to receive finasteride 5 mg/day (n=768), doxazosin 4 or 8 mg/day (n=756), the combination of finasteride 5 mg/day and doxazosin 4 or 8 mg/day* (n = 786), or placebo (n=737).
The mean patient age at randomization was 62.6 years (±7.3 years). The mean duration of BPH symptoms was 4.7 years (±4.6 years). Patients had moderate to severe BPH symptoms at baseline with a mean AUA symptom score of approximately 17 out of 35 points.
The primary endpoint was time from randomization to clinical progression of BPH, defined as the first occurrence of any of the following events: a ≥ 4 point confirmed increase from baseline in symptom score, acute urinary retention, BPH-related renal insufficiency (creatinine rise), recurrent urinary tract infections or urosepsis, or incontinence. Compared to placebo, treatment with finasteride, doxazosin, or combination therapy resulted in a significant reduction in the risk of clinical progression of BPH by 34%, 39% and 67% respectively. Combination therapy reduced the risk of clinical progression of BPH to a significantly greater extent than either finasteride or doxazosin alone, which were not significantly different from each other (see Figure 3). The majority of the events (274 out of 351) that constituted BPH progression were confirmed ≥ 4 point increases in symptom score; the risk of symptom score progression was reduced by 30%, 46% and 64%in the finasteride, doxazosin, and combination groups- respectively, compared to placebo (9.6% for finasteride, 7.8% for doxazosin, 5.2% for the 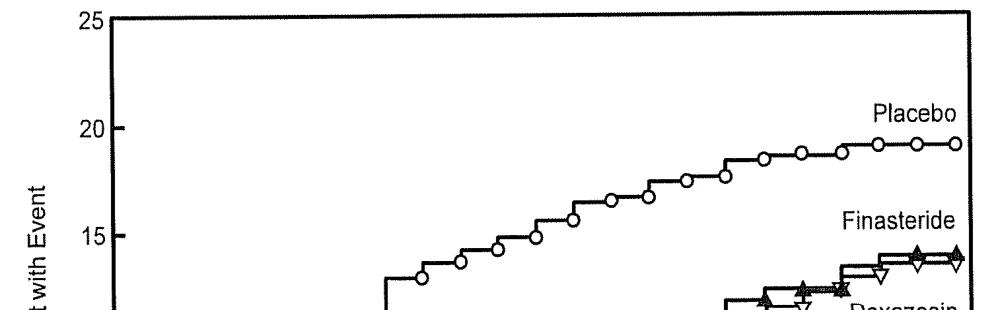
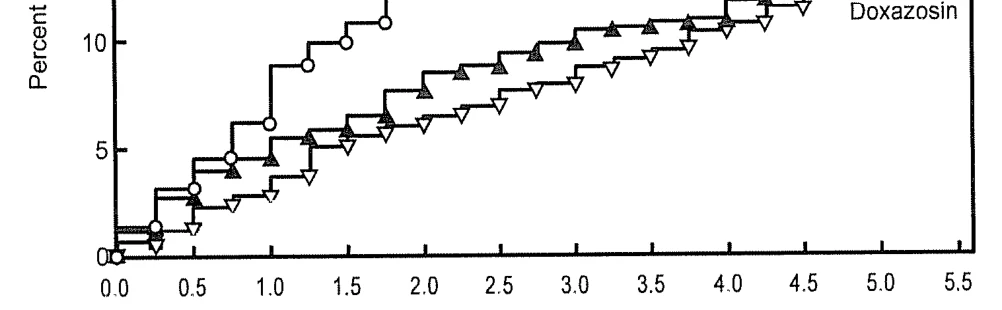 TEVA-FINASTERIDE (Finasteride Tablets) Page 23 of 35 combination and 13.6% for the placebo). Treatment with finasteride, doxazosin or the combination reduced the mean symptom score from the baseline at year 4 (see Table 5).
Figure 3 Cumulative Incidence of Clinical Progression of BPH by Treatment Group
Study Time (years)
Table 5 Change From Baseline in AUA Symptom Score by Treatment Group at Year 4 in
MTOPS
| Placebo N=534 | Doxazosin N=582 | Finasteride N=565 | Combination N=598 | |
| Baseline Mean (SD) | 16.8 (6.0) | 17.0 (5.9) | 17.1 (6.0) | 16.8 (5.8) |
Mean Change AUA Symptom Score (SD) | -4.9 (5.8) | -6.6 (6.1) | -5.6 (5.9) | -7.4 (6.3) |
| Comparison to Placebo (95% CI) | -1.8 (-2.5, -1.1) | -0.7 (-1.4, 0.0) | -2.5 (-3.2, -1.8) | |
Comparison to Doxazosin alone (95% CI) | -0.7 (-1.4, 0.0) | |||
Comparison to Finasteride alone (95% CI) | -1.8 (-2.5, -1.1) |
In MTOPS, the risk of developing acute urinary retention was reduced by 67% and 79% in the finasteride and combination groups respectively, compared to the placebo group (0.8% for finasteride, 0.5% for combination and 2.4% for placebo). Also, the risk of requiring BPH-related TEVA-FINASTERIDE (Finasteride Tablets) Page 24 of 35 invasive therapy was reduced by 64% and 67% in the finasteride and combination groups respectively, compared to the placebo group (2% for finasteride, 1.8% for the combination and 5.4% for placebo).
The results of MTOPS confirm the findings of the 4-year placebo-controlled study PLESS that treatment with finasteride reduces the risk of acute urinary retention and the need for BPH-related surgery. The results of MTOPS further demonstrate that the combination of finasteride and doxazosin reduces the risk of BPH progression to a significantly greater extent than either therapy administered alone.
Additional Clinical Trials
Urodynamic effects of finasteride in the treatment of bladder outlet obstruction due to BPH were assessed by invasive techniques in a 24-week, double-blind, placebo-controlled study of 36 patients with moderate to severe symptoms of urinary obstruction and a maximum flow rate of less than 15 mL/s. Relief of obstruction, as evidenced by significant improvement in detrusor pressure and increased mean flow rate, was demonstrated in patients treated with 5 mg finasteride compared to placebo.
The effect of finasteride on the volume of the peripheral and periurethral zones of the prostate in 20 men with BPH was evaluated by MRI in a one-year, double-blind, placebo-controlled study. Patients treated with finasteride, but not those treated with placebo, experienced a significant decrease [11.5 ± 3.2 mL (SE)] in total gland size, largely accounted for by a reduction [6.2 ± 3 mL] in the size of the periurethral zone. Since the periurethral zone is responsible for outflow obstruction, this reduction may account for the beneficial clinical response observed in these patients.
Information from a recently completed 7-year placebo-controlled trial that enrolled 18,882 men ≥ 55 years of age, with a normal digital rectal examination and a PSA of ≤ 3.0 ng/mL, may be relevant for men currently being treated with finasteride for BPH (see 8 ADVERSE REACTIONS, 8.2 Clinical Trial Adverse Reactions, Other Long Term Data).
TEVA-FINASTERIDE (Finasteride Tablets) Page 25 of 35
14.2 Comparative Bioavailability Studies
A randomized, two-treatment, crossover comparative bioavailability study of Finasteride 5 mg tablets (Teva Canada Ltd., manufactured by Teva Pharmaceutical Works Ltd.) and Proscar® 5 mg tablets (Merck Frosst Canada Ltd., Canada) administered as a single unit dose (1 x 5mg) was conducted in healthy, adult male subjects under fasting conditions.
Comparative bioavailability data from the 29 subjects who were included in the statistical analysis are summarized in the table below:
Finasteride (1 x 5 mg) From measured data Geometric Mean Arithmetic Mean (CV %) | ||||
| Parameter | Test1 | Reference2 | % Ratio of Geometric Means | 90% Confidence Interval |
AUCT (ng.h/mL) | 262.66 282.39 (35) | 248.31 262.54 (32) | 105.8 | 100.8 – 111.0 |
AUCI (ng.h/mL) | 283.57 314.04 (47) | 267.80 289.56 (41) | 105.9 | 100.7- 111.3 |
Cmax (ng/mL) | 36.20 37.91 (24) | 36.90 37.75 (19) | 98.1 | 94.5 - 101.9 |
Tmax3 (h) | 2.07 (1.0 – 4.0) | 1.69 (1.0 – 4.0) | ||
T½4 (h) | 6.18 (39.9) | 6.06 (36.5) | ||
1 Teva-Finasteride 5 mg Tablets (manufactured for Teva Canada by Teva Pharmaceutical Works Limited)
2 Proscar® 5 mg Tablets (Merck Frosst Canada Ltd.), purchased in Canada 3 Expressed as median (range) only
4 Expressed as the arithmetic mean (CV%) only
TEVA-FINASTERIDE (Finasteride Tablets) Page 26 of 35
15 MICROBIOLOGY
No microbiological information is required for this drug product.
16 NON-CLINICAL TOXICOLOGY
The ability of finasteride to inhibit 5 alpha-reductase and block the formation of DHT in vivo was demonstrated using intact male rats and dogs. Studies were designed to demonstrate a decrease in prostatic levels of DHT or shrinkage in prostate size. Four hours after receiving a subcutaneous injection of 0.1 mg finasteride, rats showed a decrease in the concentration of DHT in the prostate. In dogs, treatment with finasteride 1 mg/kg given orally in four divided doses over an 18 hour period showed a reduction in the prostatic DHT concentration 6 hours after the final dose. These studies demonstrated that finasteride is active in vivo in blocking the formation of DHT.
The decreased levels of DHT also resulted in a decrease in prostate size. Prostate shrinkage was seen in intact mature dogs which received 1 mg/kg/day of finasteride by mouth for six weeks. A comparison of pre and post-treatment prostate volumes showed that finasteride induced over 40% reduction in prostate size. A similar effect was noted in immature castrated male rats treated with testosterone. Finasteride, at oral doses of 0.1 mg/day, significantly inhibited the growth effect of exogenous testosterone on the accessory sex glands. This response is due to the specific inhibition of 5 alpha-reductase as 2.5 mg/day of finasteride failed to block the ability of exogenous DHT to stimulate growth of the seminal vesicles and ventral prostate in treated animals.
Finasteride has no direct anti-androgen activity as shown by its lack of affinity for the androgen receptor in rat prostate cytosol. Concentrations of finasteride as high as 10-4M did not prevent the binding of 3H-DHT whereas unlabelled DHT inhibited the binding with an IC50 of 2.9 nM.
Standard assays conducted in rats, mice and rabbits demonstrated that finasteride does not inhibit gonadotropin secretion or exhibit any antiestrogenic, uterotropic, antiprogestational, androgenic or progestational activity. These data are consistent with finasteride's acting as a specific 5 alpha-reductase inhibitor with no other hormonal effects.
In a hepatotoxicity test, 40 mg/kg/day of finasteride was given orally to dogs for 28 days. Venous blood was analyzed for ALT (SGPT) and AST (SGOT). Neither transaminase was increased, illustrating that finasteride did not cause liver damage.
Ancillary pharmacology studies to assess effects on organ systems and biological parameters were conducted with finasteride. No important changes were seen in renal, gastric and respiratory functions in dogs, nor in the cardiovascular system of dogs and rats.
TEVA-FINASTERIDE (Finasteride Tablets) Page 27 of 35
General Toxicology:
Table 6 -Acute Toxicity
| Species | Sex | Finasteride Route | LD50 mg/kg |
| Mouse | Male | Oral | 596 |
| Female | Oral | 486 | |
| Male | Intraperitoneal | 391 | |
| Female | Intraperitoneal | 372 | |
| Rat | Male | Oral | 967 |
| Female | Oral | 418 | |
| Male | Intraperitoneal | 1027 | |
| Female | Intraperitoneal | 885 | |
| Male | Subcutaneous | >2000 | |
| Female | Subcutaneous | >2000 | |
| Dog | Male | Oral | >1000 |
Subacute and Chronic Toxicity Studies
The nature of the treatment-related changes in laboratory animals treated with finasteride are shown in Table 7.
Table 7 Finasteride ; Target Organs Observed in Animal Studies
| Treatment-Related Changes | Species | No Effect Dose (mg/kg/day) |
| Epididymal vacuolation (head) | Rat | 0.1 |
| Testes - Leydig cell hyperplasia | Rat Mouse | 20 2.5 |
| Mouse | 25 |
| Liver - increased weight | Mouse Rat Dog | 2.5 5 15 |
| Thyroid - increased weight | Rat | 5 |
| Increased serum alkaline phosphatase | Dog | 5 |
TEVA-FINASTERIDE (Finasteride Tablets) Page 28 of 35 For most of the treatment-related changes seen in laboratory animals, a clear no-effect dose has been defined. Furthermore, most of the observed treatment-related effects can be categorized under three broad headings based on the current understanding of the drug-induced changes (Table 8).
Table 8 Treatment; Related Changes Seen in Laboratory Animals
| Treatment – Related Changes | Species |
| Rats, mice, dogs Rats Rats Rats |
| Rats, mice mice |
| Rats, mice, dogs Rats |
Carcinogenicity:
No evidence of a tumorigenic effect was observed in a 24-month study in rats receiving doses of finasteride of up to 320 mg/kg/day (3200 times the recommended human dose of 5 mg/day).
In a 19-month carcinogenicity study in mice, a statistically significant (p ≤ 0.05) increase in the incidence of testicular Leydig cell adenoma was observed at a dose of 250 mg/kg/day (2500 times the recommended human dose of 5 mg/day); no adenomas were seen in mice given 2.5 or 25 mg/kg/day (25 and 250 times the recommended human dose of 5 mg/day, respectively) (Table 8).
In mice, at a dose of 25 mg/kg/day, and in rats, at a dose of ≥ 40 mg/kg/day (250 and ≥ 400 times the recommended human dose of 5 mg/day, respectively), an increase in the incidence of Leydig cell hyperplasia was observed. A positive correlation between the proliferative changes of the Leydig cells and the increase in serum luteinizing hormone (LH) levels (2-3 fold above control) has been demonstrated in both rodent species treated with high doses of finasteride (Table 7).
No drug-related Leydig cell changes were seen in either rats or dogs treated with finasteride for one year, at doses of 20 mg/kg/day and 45 mg/kg/day (200 and 450 times the recommended human dose of 5 mg/day, respectively), or in mice treated for 19 months, at a dose of 2.5 mg/kg/day (25 times the recommended human dose of 5 mg/day) (Table 7).
Genotoxicity:
TEVA-FINASTERIDE (Finasteride Tablets) Page 29 of 35 No evidence of mutagenicity was observed in an in vitro bacterial mutagenesis assay, a mammalian cell mutagenesis assay, or in an in vitro alkaline elution assay. In an in vitro chromosome aberration assay, when Chinese hamster ovary cells were treated with high concentrations (450-550 µmol/L) of finasteride, there was a slight increase in chromosome aberrations. These concentrations correspond to 4000-5000 times the peak plasma levels in man given a total dose of 5 mg. Furthermore, the concentrations (450-550 µmol/L) used in the in vitro studies are not achievable in a biological system. In an in vivo chromosome aberration assay in mice, no treatment-related increases in chromosome aberration were observed with finasteride at the maximum tolerated dose (250 mg/kg/day; 2500 times the recommended human dose of 5 mg/day).
Reproductive and Developmental Toxicology:
In sexually mature male rabbits treated with finasteride at 80 mg/kg/day (800 times the recommended human dose of 5 mg/day) for up to 12 weeks, no effect on fertility, sperm count or ejaculate volume was seen.
In sexually mature male rats treated with the same dose of finasteride, there were no significant effects on fertility after 6 or 12 weeks of treatment; however, when treatment was continued for up to 24 or 30 weeks, there was an apparent decrease in fertility and fecundity, and an associated significant decrease in the weights of the seminal vesicles and prostate. All these effects were reversible within 6 weeks of discontinuation of treatment.
The decrease in fertility in rats treated with finasteride is due, at least in large part, to its effect on accessory sex organs (prostate and seminal vesicles) with failure to form a seminal plug. The seminal plug is essential for normal fertility in rats and is not relevant in humans who do not form copulatory plugs. No drug-related effect on testes or on mating performance has been seen in rats or rabbits.
Dose-dependent development of hypospadias was observed in the male offspring of pregnant rats given finasteride at doses ranging from 100 µg/kg/day to 100 mg/kg/day (1 to 1000 times the recommended human dose of 5 mg/day) at an incidence of 3.6 to 100%. Additionally, pregnant rats produced male offspring with decreased prostatic and seminal vesicular weights, delayed preputial separation, and transient nipple development when given finasteride at doses ≥30µg/kg/day (≥ 30% of the recommended human dose of 5 mg/day) and decreased anogenital distance when given finasteride in doses ≥ 3 µg/kg/day (≥ 3% of the recommended human dose of 5 mg/day). The critical period during which these effects can be induced has been defined in rats as days 16-17 of gestation.
The changes described above are expected pharmacological effects of Type II 5 alpha-reductase inhibitors. Many of the changes, such as hypospadias, observed in male rats exposed in utero to finasteride, are similar to those reported in male infants with a genetic deficiency of Type II 5 alpha-reductase. No effects were seen in female offspring exposed in utero to any dose of finasteride.
TEVA-FINASTERIDE (Finasteride Tablets) Page 30 of 35 Administration of finasteride to rats during the late gestation and lactation period results in slightly decreased fertility in first generation male offspring (3 mg/kg/day; 30 times the recommended human dose of 5 mg/day). No developmental abnormalities have been observed in first generation male or female offspring resulting from mating finasteride-treated male rats (80 mg/kg/day; 800 times the recommended human dose of 5 mg/day) with untreated females.
No evidence of malformations has been observed in rabbit fetuses exposed to finasteride in utero from days 6-18 of gestation at doses up to 100 mg/kg/day (1000 times the recommended human dose of 5 mg/day).
The in utero effects of finasteride exposure during the period of embryonic and fetal development were evaluated in the rhesus monkey (gestation days 20-100), a species more predictive of human development than rats or rabbits. Intravenous administration of finasteride to pregnant monkeys at doses as high as 800 ng/day (at least 60 to 120 times the highest estimated exposure of pregnant women to finasteride from semen of men taking 5 mg/day) resulted in no abnormalities in male fetuses. In confirmation of the relevance of the rhesus model for human fetal development, oral administration of a very high dose of finasteride (2 mg/kg/day; 20 times the recommended human dose of 5 mg/day or approximately 1-2 million times the highest estimated exposure to finasteride from semen of men taking 5 mg/day) to pregnant monkeys resulted in external genital abnormalities in male fetuses. No other abnormalities were observed in male fetuses and no finasteride-related abnormalities were observed in female fetuses at any dose.
17 SUPPORTING PRODUCT MONOGRAPHS
- 1.
Proscar® (Finasteride Tablets 5 mg), Control Number - 275151, Product Monograph,
Organon Canada Inc., (NOV 24, 2023).