


Product Monograph - Trandate
Recent Major Label Changes
Not applicable at time of the most recent authorization
TABLE OF CONTENTS
Sections or subsections that are not applicable at the time of authorization are not listed.
Recent Major Label Changes .................................................................................................... 2
TABLE OF CONTENTS ............................................................................................................... 2
Part I: Healthcare Professional Information ............................................................................. 4
- 1.
Indications ................................................................................................................... 4
1.1. Pediatrics ............................................................................................................... 4
1.2. Geriatrics ............................................................................................................... 4
- 2. Contraindications ......................................................................................................... 4
- 3. Serious Warnings and Precautions Box ........................................................................ 5
- 4.
Dosage and Administration .......................................................................................... 5
4.1. Dosing Considerations ........................................................................................... 5
4.2. Recommended Dose and Dosage Adjustment ...................................................... 5
4.2.1. Discontinuing Treatment ................................................................................... 5
4.4. Administration ....................................................................................................... 5
4.5. Missed Dose .......................................................................................................... 6
- 5. Overdose...................................................................................................................... 6
- 6. Dosage Forms, Strengths, Composition, and Packaging ................................................ 7
- 7.
Warnings and Precautions ............................................................................................ 7
General .............................................................................................................................. 7
Cardiovascular ................................................................................................................... 7
Endocrine and Metabolism ............................................................................................... 8
Hepatic/Biliary/Pancreatic ................................................................................................ 8
Immune ............................................................................................................................. 9
Monitoring and Laboratory Tests ...................................................................................... 9
Ophthalmologic ................................................................................................................. 9
Peri-Operative Considerations .......................................................................................... 9
Skin .................................................................................................................................... 9
7.1. Special Populations .............................................................................................. 10
7.1.1. Pregnant Women ............................................................................................ 10
7.1.2. Breastfeeding .................................................................................................. 10
7.1.3. Pediatrics ......................................................................................................... 10
7.1.4. Geriatrics ......................................................................................................... 10
- 8.
Adverse Reactions ...................................................................................................... 10
8.1. Adverse Reaction Overview ................................................................................. 10
8.2. Clinical Trial Adverse Reactions ........................................................................... 10
8.4. Abnormal Laboratory Findings: Hematologic, Clinical Chemistry and Other Quantitative Data ............................................................................................................ 11
8.5. Post-Market Adverse Reactions .......................................................................... 11
- 9.
Drug Interactions ....................................................................................................... 12
9.2. Drug Interactions Overview ................................................................................. 12
9.4. Drug-Drug Interactions ........................................................................................ 12
9.5. Drug-Food Interactions ........................................................................................ 12
9.6. Drug-Herb Interactions ........................................................................................ 12
9.7. Drug-Laboratory Test Interactions ....................................................................... 12
- 10.
Clinical Pharmacology ................................................................................................ 13
10.1. Mechanism of Action ....................................................................................... 13
10.2. Pharmacodynamics ......................................................................................... 13
10.3. Pharmacokinetics ............................................................................................ 13
- 11. Storage, Stability and Disposal ................................................................................... 14
Part II: Scientific Information ................................................................................................. 15
- 13. Pharmaceutical Information ....................................................................................... 15
- 14.
Clinical Trials .............................................................................................................. 15
14.2. Comparative Bioavailability Studies ................................................................. 15
- 16. Non-Clinical Toxicology .............................................................................................. 16
Patient Medication Information ............................................................................................ 17
Part I: Healthcare Professional Information
1. Indications
TRANDATE (labetalol hydrochloride tablets) is indicated for:
- the treatment of hypertension.
TRANDATE is usually used in combination with other drugs, particularly a thiazide diuretic (see 4.1 Dosing Considerations and 9.2 Drug Interactions Overview).
However, TRANDATE may be used alone as an initial agent in those patients in whom, in the judgement of the healthcare professional, treatment should be started with an alpha- beta- blocker rather than with a diuretic.
TRANDATE may be used in combination with diuretics and/or other antihypertensive agents to treat severe hypertension (see 4.1 Dosing Considerations and 9.2 Drug Interactions Overview).
The combination of TRANDATE with a diuretic has been found to be compatible. Limited experience with other antihypertensive agents has not shown evidence of incompatibility with TRANDATE.
1.1. Pediatrics
Pediatrics (< 18 years of age): No data are available to Health Canada. Therefore, Health Canada has not authorized an indication for pediatric use.
1.2. Geriatrics
Geriatrics (≥ 65 years of age): Evidence from experience suggests that use in the geriatric population is associated with differences in safety or effectiveness. Therefore, lower doses of TRANDATE are likely to be required in geriatric patients (see 7.1.4 Geriatrics and 4.2 Recommended Dose and Dosage Adjustment, Geriatric patients).
2. Contraindications
TRANDATE is contraindicated in patients:
- who are hypersensitive to this drug or to any ingredient in the formulation including any non-medicinal ingredient, or component of the container. For a complete listing, see 6 Dosage Forms, Strengths, Composition and Packaging
- exhibiting sinus bradycardia or sick sinus syndrome
- with uncontrolled congestive heart failure
- with cardiogenic shock and states of hypoperfusion
- with asthma or a history of obstructive lung disease
- with greater than first degree atrioventricular (AV) block
- with severe peripheral arterial circulatory disorders
3. Serious Warnings and Precautions Box
Severe hepatocellular injury
- Injury has occurred after both short term and long-term treatment with labetalol hydrochloride and may be slowly progressive despite minimal symptomatology. The hepatic injury is usually reversible but rare cases of hepatic necrosis and death have been reported. Appropriate laboratory testing should be performed at regular intervals during TRANDATE therapy (see 7 Warnings and Precautions, Hepatic/Biliary/Pancreatic and Monitoring and Laboratory Tests).
4. Dosage and Administration
4.1. Dosing Considerations
Optimal doses are usually lower in patients also receiving a diuretic and/or other antihypertensive agents since an additive antihypertensive effect can be expected.
4.2. Recommended Dose and Dosage Adjustment
The dosage of TRANDATE must always be adjusted in accordance with the individual requirements of the patient. The recommended initial dose is 100 mg twice daily whether used alone or with a diuretic. Thereafter, the dose should be adjusted semi-weekly or weekly according to the response (see 7 Warnings and Precautions, General).
The usual maintenance dose is 200 mg to 400 mg twice daily. Patients may require up to 1200 mg per day, in two divided doses.
Hepatic Impairment: Patients with liver function impairment will likely require lower doses since metabolism of the drug will be diminished.
Geriatrics: Lower doses of TRANDATE are likely to be required in elderly patients (see 7.1.4 Geriatrics).
Pediatrics: Health Canada has not authorized an indication for pediatric use.
4.2.1. Discontinuing Treatment
When discontinuation of TRANDATE is planned in patients with angina pectoris, the dosage should be gradually reduced over a period of about two weeks and the patient should be carefully observed. The same frequency of administration should be maintained. In situations of greater urgency, TRANDATE therapy should be discontinued stepwise and under conditions of closer observation.
If angina markedly worsens or acute coronary insufficiency develops, it is recommended that treatment with TRANDATE be re-instituted promptly, at least temporarily.
4.4. Administration
TRANDATE should be taken preferably after food.
4.5. Missed Dose
If a patient misses a dose, advise them to take the dose as soon as possible and continue with their regular schedule. However, a patient should not take 2 doses the same day.
5. Overdose
Symptoms
The signs and symptoms associated with TRANDATE overdosage are excessive hypotension which is posture-sensitive, and sometimes, excessive bradycardia.
Treatment
Patients should be laid supine and their legs raised, if necessary. Gastric lavage or pharmacologically-induced emesis (using syrup of ipecac) is useful for removal of the drug shortly after ingestion. Hemodialysis removes less than 1% of circulating labetalol, and is therefore not recommended.
If overdose occurs, provide general supportive and specific symptomatic treatment. Based on expected pharmacologic actions and recommendations for other beta-blockers, the following additional measures should be employed if necessary, including stopping TRANDATE when clinically warranted:
Excessive bradycardia: Administer atropine intravenously to induce vagal blockage. If bradycardia persists, isoproterenol may be administered cautiously. In refractory cases, the use of a cardiac pacemaker may be considered.
Congestive heart failure: Conventional therapy with cardiac glycosides and diuretics.
Hypotension: Administer vasopressors, e.g.: norepinephrine.
Bronchospasm: Administer a beta2-stimulating agent and/or a theophylline preparation.
Heart block (second or third degree): Monitor and treat with isoproterenol infusion. Under some circumstances, transthoracic or transvenous pacemaker placement may be necessary.
Hypoglycemia: Administer intravenous glucose. Repeated dose of intravenous glucose or possibly glucagon may be required.
Oliguric renal failure has been reported after massive overdosage of TRANDATE (labetalol hydrochloride) orally. In one case, the use of dopamine to increase blood pressure may have aggravated the renal failure.
For the most recent information in the management of a suspected drug overdose, contact your regional poison control centre or Health Canada’s toll-free number, 1-844 POISON-X (1-844-764-7669).
- 6. Dosage Forms, Strengths, Composition, and Packaging
Table 1 – Dosage Forms, Strengths, and Composition
TRANDATE is a capsule-shaped tablet available in two strengths, 100 mg and 200 mg of labetalol hydrochloride and showing the following distinguishable characteristics:
- 100 mg tablets: each film-coated tablet is orange, scored and engraved “LAB 100” on one side and “PLB” on the other side
- 200 mg tablets: each film-coated tablet is white, scored and engraved “LAB 200” on one side and “PLB” on the other side.
TRANDATE is supplied in bottles of 100 tablets.
7. Warnings and Precautions
(Please see 3 Serious Warnings and Precautions Box)
General
Postural hypotension and syncope may occur in patients treated with TRANDATE, particularly if the initial dose is too high or if dose titration is too rapid (see 4.2 Recommended Dose and Dosage Adjustment). Treatment should start with small doses without additional alpha- or beta-adrenergic blocking drugs.
Cardiovascular
Abrupt cessation of therapy: Patients with angina should be warned against abrupt discontinuation of beta-adrenergic blocking agents. There have been reports of severe exacerbation of angina, and of myocardial infarction or ventricular arrhythmias occurring in patients with angina pectoris, following abrupt discontinuation of therapy. The last two complications may occur with or without preceding exacerbation of angina pectoris.
Cardiac failure: Cardiac failure should be controlled with digitalis and diuretics before TRANDATE treatment is initiated. TRANDATE should not be given to patients with digitalis-resistant heart failure. Sympathetic stimulation is a vital component supporting circulatory function in congestive heart failure and inhibition with beta-blockade always carries the potential hazard of further depressing myocardial contractibility and precipitating cardiac failure. A few patients developed heart failure while on TRANDATE. Therefore, administration of TRANDATE to patients with controlled failure or those likely to develop heart failure must be
| Route of Administration | Dosage Form / Strength/Composition | Non-medicinal Ingredients |
| oral | tablet, 100 mg and 200 mg of labetalol hydrochloride | colloidal silicon dioxide, croscarmellose sodium, D&C Yellow #10 Aluminum Lake (100 mg tablets only), hydroxypropyl cellulose, hydroxypropyl methylcellulose, magnesium stearate, methylcellulose, polyethylene glycol 8000, purified water, Sunset Yellow Aluminum Lake (100 mg tablets only) and titanium dioxide. |
carried out under careful supervision. The drug does not abolish the inotropic action of digitalis on heart muscle.
Sinus bradycardia: Severe sinus bradycardia may occur with the use of TRANDATE from unopposed vagal activity remaining after blockade of beta1-adrenergic receptors; in such cases, dosage should be reduced.
Severe peripheral artery disorders: Beta-blockers may aggravate the symptoms of severe peripheral arterial circulatory disorders, mainly due to their blood pressure lowering effect. Caution should be exercised in individuals with such disorders.
Non-dihydropyridine calcium channel blockers: The combination of non-dihydropyridine calcium channel blockers of the verapamil and diltiazem type and beta-blockers warrants caution since additive effects on myocardial contractility, heart rate and AV conduction have been observed. Close medical supervision is recommended (see 9.2 Drug Interactions Overview).
Endocrine and Metabolism
Diabetes and hypoglycemia: TRANDATE should be used with caution in patients subject to hypoglycemic episodes since beta-receptor blocking drugs may mask some of the manifestations of hypoglycemia, particularly tachycardia and may enhance hypoglycemia in patients prone to this condition.
Also, diabetics on insulin or oral hypoglycemic medication may have an increased tendency towards hypoglycemia when treated with these drugs. Patients subject to spontaneous hypoglycemia and diabetic patients receiving insulin or oral hypoglycemic agents should be advised about these possibilities.
Thyrotoxicosis: In patients with thyrotoxicosis, possible deleterious effects from long-term use of TRANDATE have not been adequately appraised. Beta-blockade may mask the clinical signs of continuing hyperthyroidism or complications, and give a false impression of improvement. Therefore, these patients should be carefully monitored for thyroid function. Abrupt withdrawal of TRANDATE may be followed by an exacerbation of the symptoms of hyperthyroidism or may precipitate a thyroid storm.
Pheochromocytoma: While TRANDATE has been shown to be effective in lowering the blood pressure and relieving symptoms in patients with pheochromocytoma, paradoxical hypertensive responses have been reported in a few patients with this tumour. Use caution when administering TRANDATE to patients with known or suspected pheochromocytoma.
Hepatic/Biliary/Pancreatic
There have been rare reports of severe hepatocellular injury with TRANDATE therapy. Injury has occurred after both short term and long-term treatment and may be slowly progressive despite minimal symptomatology. The hepatic injury is usually reversible but rare cases of hepatic necrosis and death have been reported. Appropriate laboratory testing should be performed at regular intervals during TRANDATE therapy (see 7 Warnings and Precautions, Monitoring and Laboratory Tests). Tests should also be done at the first sign or symptom of liver dysfunction (e.g.:, pruritus, dark urine, persistent anorexia, jaundice, right upper quadrant tenderness or unexplained flu-like symptoms). If there is laboratory evidence of liver injury or the patient is jaundiced, TRANDATE should be stopped and not restarted.
Immune
Risk of anaphylactic reactions: While taking beta-blockers, patients with a history of severe anaphylactic reactions to a variety of allergens may be more reactive to repeated accidental, diagnostic, or therapeutic challenge. There may be increased difficulty in treating an allergic-type reaction in patients on beta-blockers. In these patients, the reaction may be more severe due to pharmacological effects of beta-blockers and problems with fluid changes. Epinephrine should be administered with caution since it may not have its usual effects in the treatment of anaphylaxis. On the one hand, larger doses of epinephrine may be needed to overcome the bronchospasm, while on the other, these doses can be associated with excessive alpha-adrenergic stimulation with consequent hypertension, reflex bradycardia and heart block and possible potentiation of bronchospasm. Alternatives to the use of large doses of epinephrine include vigorous supportive care such as fluids and the use of beta agonists including parenteral salbutamol or isoproterenol to overcome bronchospasm and norepinephrine to overcome hypotension.
Monitoring and Laboratory Tests
Appropriate liver function laboratory testing should be performed at regular intervals during TRANDATE therapy (see 7 Warnings and Precautions, Hepatic/Biliary/Pancreatic).
Ophthalmologic
Animal studies have shown that labetalol binds to the melanin of the uveal tract. The significance of this in humans is not known but periodic ophthalmic examinations are advisable while the patient is taking TRANDATE.
Peri-Operative Considerations
Patients undergoing surgery: The management of patients being treated with beta-blockers and undergoing surgery is controversial. Although beta-adrenergic-receptor blockade impairs the ability of the heart to respond to beta-adrenergically mediated reflex stimuli, abrupt discontinuation of therapy with TRANDATE may be followed by severe complications (see 7 Warnings and Precautions, Cardiovascular; Endocrine and Metabolism; Immune). Some patients receiving beta-adrenergic-blocking agents have been subject to protracted severe hypotension during anesthesia. Difficulty in restarting and maintaining the heartbeat has also been reported. For these reasons, in patients with angina undergoing elective surgery, TRANDATE should be withdrawn gradually following the recommendation given under 4.2.1 Discontinuing Treatment.
In emergency surgery, since TRANDATE is a competitive inhibitor of beta-adrenergic-receptor agonists, its effects may be reversed, if necessary, by sufficient doses of such agonists as isoproterenol.
Skin
Oculomucocutaneous syndrome: Various skin rashes and conjunctival xerosis have been reported with beta-blockers. A severe syndrome (oculomucocutaneous syndrome) whose signs include conjunctivitis sicca and psoriasiform rashes, otitis, and sclerosing serositis has occurred with the chronic use of one beta-adrenergic blocking agent (practolol). This syndrome has not been observed in association with TRANDATE or any other such agent. However, healthcare professionals should be alert to the possibility of such reactions and should discontinue treatment in the event that they occur.
7.1. Special Populations
7.1.1. Pregnant Women
Although no teratogenic effects were seen in animal testing, the safety of the use of TRANDATE during pregnancy has not been established. Labetalol crosses the placental barrier in women and has been found to bind to the eyes of fetal animals. TRANDATE should be used in pregnant women only if the expected benefit to the mother justifies the potential risk to the fetus.
7.1.2. Breastfeeding
Labetalol has been found in the breast milk of lactating women. If the use of TRANDATE is considered essential, then mothers should stop nursing.
7.1.3. Pediatrics
Pediatrics (< 18 years of age): No data are available to Health Canada; therefore, Health Canada has not authorized an indication for pediatric use.
7.1.4. Geriatrics
Geriatrics (≥ 65 years of age): The bioavailability and half-life of TRANDATE are increased in the elderly. In addition, the hypotensive response is greater in this age group following administration. Therefore, lower doses of TRANDATE are likely to be required in elderly patients (see 4.2 Recommended Dose and Dosage Adjustment, Geriatric).
8. Adverse Reactions
8.1. Adverse Reaction Overview
The most serious reported adverse effects of TRANDATE are severe postural hypotension, jaundice and bronchospasm.
8.2. Clinical Trial Adverse Reactions
Clinical trials are conducted under very specific conditions. The adverse reaction rates observed in the clinical trials therefore, may not reflect the rates observed in practice and should not be compared to the rates in the clinical trials of another drug. Adverse reaction information from clinical trials may be useful in identifying and approximating rates of adverse drug reactions in real-world use.
In well controlled clinical trials, the most common transient adverse reactions reported at routinely administered therapeutic doses, were postural hypotension and/or dizziness (16.9%), fatigue/malaise (13.1%), and headache (8.0%). Other transient effects include acute retention of urine and difficulty in micturition. The following summarizes the adverse effects reported.
Cardiovascular: postural hypotension/dizziness (16.9%), angina pectoris (3.2%), Raynaud's phenomenon (3.2%), pedal edema (1.9%), palpitations (1.3%), bradycardia (< 1.0%)
Gastrointestinal: nausea/vomiting (6.1%), dyspepsia (1.9%), constipation (1.6%), dry mouth/sore throat (1.6%)
Respiratory: dyspnea (3.8%), nasal congestion (1.3%)
Dermatological: drug rash (3.2%), paresthesia (especially "scalp tingling") (3.8%), pruritus (0.6%) and angioedema
Urogenital: impotence (2.2%), failure of ejaculation (0.6%), dysuria (0.6%)
Musculoskeletal: aches/pains (3.5%), muscle cramps (1.3%)
Central Nervous System: fatigue/malaise (13.1%), headache (8.0%), depression (2.6%), loss of libido (1.3%), dreaming (1.3%)
Miscellaneous: visual blurring (4.2%), epistaxis (1.6%)
In addition, in the more extensive trials, bronchospasm and severe bradycardia were reported with an incidence of less than 1%. There are rare reports of raised liver function tests, jaundice (both hepatic and cholestatic), and hepatic necrosis (see 7 Warnings and Precautions, Hepatic/Biliary/Pancreatic).
8.4. Abnormal Laboratory Findings: Hematologic, Clinical Chemistry and Other Quantitative Data
Occasional elevations of serum transaminases and blood urea have been reported following oral administration.
8.5. Post-Market Adverse Reactions
Other published or unpublished reports describe other rare, isolated adverse events in patients who were taking TRANDATE (oral or injectable), as follows: bronchospasm and reduction in peak expiratory flow rate (PEFR), difficulty in micturition including acute urinary retention, ejaculatory failure, Peyronie's disease, toxic myopathy, tremor, taste distortion, hypersensitivity, hypoesthesia, rashes of various types such as generalized maculopapular, lichenoid, urticarial, bullous lichen planus, psoriasiform, facial erythema, reversible alopecia and very rarely drug fever. A skin lesion resembling disseminated lupus erythematosus occurred rarely in one patient receiving a high dose of TRANDATE. There are rare reports of patients who developed lupus-like syndromes while on TRANDATE which cleared upon discontinuation of treatment. Positive antinuclear factor and antimitochondrial antibodies have been reported in patients receiving the drug, but the significance of these findings is not clear.
Because these reactions are reported voluntarily from a population of uncertain size, it is not always possible to reliably estimate their frequency or establish a causal relationship to drug exposure.
9. Drug Interactions
9.2. Drug Interactions Overview
Care should be taken if TRANDATE is used concomitantly with either Class I antiarrhythmic agents or calcium antagonists of the verapamil class since these drugs may potentiate the cardiac depressant activities of TRANDATE (see 7 Warnings and Precautions, Cardiovascular).
When used with diuretics and/or other antihypertensive agents the dose of TRANDATE must be appropriately adjusted (see 4.1 Dosing Considerations).
9.4. Drug-Drug Interactions
Halothane: TRANDATE and halothane have additive hypotensive effects. High doses of halothane (3%) with TRANDATE predispose the patient to the myocardial depressant effects of halothane and an undesirable reduction in myocardial performance. The anaesthesiologist should be informed when a patient is receiving TRANDATE.
Nitroglycerin: TRANDATE blunts the reflex tachycardia produced by nitroglycerin without preventing its hypotensive effect. When TRANDATE is used with nitroglycerin in patients with angina pectoris, additional antihypertensive effects may occur.
Cimetidine: Cimetidine has been shown to increase the oral bioavailability of TRANDATE. As cimetidine might be given to patients with hypertension also receiving TRANDATE, special care should be used in establishing the dose required for blood pressure control in such patients.
Tricyclic antidepressants: In one survey, 2.3% of patients taking TRANDATE in combination with tricyclic antidepressants experienced tremor as compared to 0.7% reported to occur with TRANDATE alone. The contribution of each of the treatments to this adverse reaction is unknown, but the possibility of a drug interaction cannot be excluded.
Fingolimod: Concomitant use of fingolimod with beta blockers may potentiate bradycardic effects and is not recommended. Where such co-administration is considered necessary, appropriate monitoring at treatment initiation, i.e. at least overnight monitoring, is recommended.
9.5. Drug-Food Interactions
When taken with food, the bioavailability of unchanged drug is increased although peak plasma levels remain the same. TRANDATE should be taken preferably after food (see 4.1 Dosing Considerations and 10.3 Pharmacokinetics, Metabolism).
9.6. Drug-Herb Interactions
Interactions with herbal products have not been established.
9.7. Drug-Laboratory Test Interactions
The presence of a metabolite of TRANDATE in the urine may result in falsely elevated levels of urinary catecholamines when measured by a nonspecific trihydroxy indole (THI) reaction. In screening patients suspected of having a pheochromocytoma and being treated with TRANDATE, specific radioenzymatic or high-performance liquid chromatographic assay techniques should be used to determine levels of catecholamines or their metabolites.
10. Clinical Pharmacology
10.1. Mechanism of Action
TRANDATE is an adrenergic receptor blocking agent possessing both alpha1-(post-synaptic) and beta-receptor blocking activity. Its action on beta-receptors is four times stronger than that on alpha-receptors. It antagonizes beta1- and beta2-receptors equally.
The mechanism of the antihypertensive action of labetalol has not been fully established. It is considered that labetalol lowers blood pressure by partially blocking the alpha-adrenoreceptors in the peripheral arterioles, thus causing vasodilation and a resulting reduction of peripheral resistance. At the same time, blockade of the beta-adrenoreceptors in the myocardium prevents reflex tachycardia and subsequent elevation of cardiac output. Peripheral vasodilation is achieved with incomplete blockade of alpha-adrenoreceptors in the arterioles and the barostatic reflexes remain sufficiently active to reduce the incidence of postural hypotension.
10.2. Pharmacodynamics
At rest, labetalol slightly reduces the heart rate, increases the stroke volume but does not significantly affect cardiac output. It reduces exercise-induced increases in systolic pressure and heart rate, again without significantly influencing cardiac output.
Following oral administration to hypertensive patients, labetalol decreases plasma renin activity and aldosterone levels, both at rest and during exercise, particularly when these were elevated prior to treatment. Labetalol is significantly more efficacious in hypertensive patients with high baseline plasma noradrenaline levels.
10.3. Pharmacokinetics
Labetalol produces a significant fall in blood pressure in 1 to 4 hours after the first oral dose. The maximum blood pressure lowering effect at any particular dose level is usually achieved within 24 to 72 hours.
Absorption
Labetalol is well absorbed from the gastrointestinal tract with peak blood levels occurring 1 to 2 hours after oral dosing.
A single oral dose of 200 mg produced average peak plasma levels of 360 mcg per 100 mL.
Distribution
Rapid and extensive distribution within tissue compartments occurs after i.v. administration. The drug is approximately 50% bound to plasma proteins.
Metabolism
The drug undergoes extensive first-pass metabolism following oral administration. The bioavailability of oral compared to intravenous (i.v.) labetalol is approximately 25%. When taken with food, the bioavailability of unchanged drug is increased although peak plasma levels remain the same. The drug is metabolized mostly by conjugation with glucuronic acid; the resulting metabolite is inactive.
Elimination
Labetalol and its metabolites are rapidly excreted in urine, and via bile into the feces. The plasma half-life of labetalol is approximately 6 to 8 hours following oral administration.
Special Populations and Conditions
Hepatic impairment: In patients with chronic liver disease the oral bioavailability of labetalol is enhanced due to reduced first pass metabolism. Lower doses of TRANDATE are likely to be required in these patients (see 4 Dosage and Administration, 4.2 Recommended Dose and Dosage Adjustment, Hepatic impairment).
11. Storage, Stability and Disposal
Store between 15°C and 30°C. Keep out of reach and sight of children.
Part II: Scientific Information
13. Pharmaceutical Information
Drug Substance
Non-proprietary name of the drug substance: labetalol hydrochloride
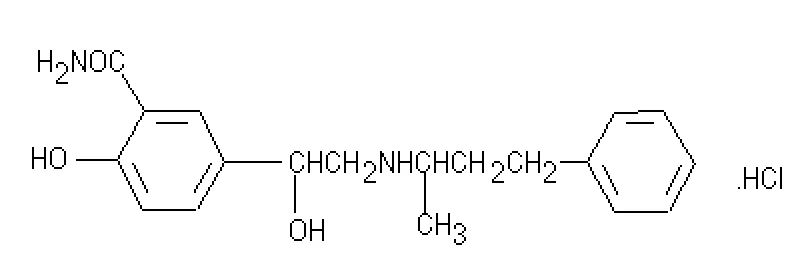
Chemical name: 2-hydroxy-5-[1-hydroxy-2-[(1-methyl-3-phenyl-propyl)amino]ethyl] benzamidehydrochloride
Molecular formula and molecular mass: C19H24N2O3•HCl and 364.9 g/mol
Structural formula:
Physicochemical properties: Labetalol hydrochloride is a white to off-white powder with a melting point around 185°C. Labetalol hydrochloride is soluble in water and in alcohol; it is insoluble in ether and chloroform; in water = 1:60, in ethanol = 1:60, in ether = almost insoluble, in chloroform = almost insoluble. The pH of a 1% w/v solution of labetalol hydrochloride is between 4.0 - 5.0.
14. Clinical Trials
14.2. Comparative Bioavailability Studies
In a clinical pharmacologic study in severe hypertensives, an initial 0.25 mg/kg injection of labetalol administered to patients in the supine position decreased blood pressure by an average of 11/7 mm Hg. Additional injections of 0.5 mg/kg at 15 minute intervals up to a total cumulative dose of 1.75 mg/kg of labetalol caused further dose-related decreases in blood pressure. Some patients required cumulative doses of up to 3.25 mg/kg. The maximal effect of each dose level occurred within 5 minutes. Following discontinuation of i.v. treatment with labetalol, the blood pressure rose gradually and progressively, approaching pretreatment baseline values within an average of 16 to 18 hours in the majority of patients.
Similar results were obtained in the treatment of patients with severe hypertension requiring urgent blood pressure reduction with an initial dose of 20 mg (which corresponds to 0.25 mg/kg for an 80 kg patient) followed by additional doses of either 40 mg or 80 mg at 10-minute intervals to achieve the desired effect or up to a cumulative dose of 300 mg.
16. Non-Clinical Toxicology
The non-clinical toxicology data, on which the original indication was authorized, is not available.