


Product Monograph - Trecondyv
RECENT MAJOR LABEL CHANGES
None.
TABLE OF CONTENTS
RECENT MAJOR LABEL CHANGES ..................................................................................... 2
TABLE OF CONTENTS .......................................................................................................... 2
PART I: HEALTH PROFESSIONAL INFORMATION ............................................................... 4
1 INDICATIONS .............................................................................................................. 4
1.1 Pediatrics............................................................................................................ 4
1.2 Geriatrics ............................................................................................................ 4
2 CONTRAINDICATIONS ............................................................................................... 4
3 SERIOUS WARNINGS AND PRECAUTIONS BOX ...................................................... 5
4 DOSAGE AND ADMINISTRATION .............................................................................. 5
4.1 Dosing Considerations ........................................................................................ 5
4.2 Recommended Dose and Dosage Adjustment..................................................... 5
4.3 Administration ..................................................................................................... 5
4.4 Reconstitution ..................................................................................................... 5
4.5 Missed Dose ....................................................................................................... 6
5 OVERDOSAGE ........................................................................................................... 6
6 DOSAGE FORMS, STRENGTHS, COMPOSITION AND PACKAGING ........................ 6
7 WARNINGS AND PRECAUTIONS............................................................................... 7
7.1 Special Populations .......................................................................................... 10
7.1.1 Pregnant Women........................................................................................... 10
7.1.2 Breast-feeding ............................................................................................... 10
7.1.3 Pediatrics ...................................................................................................... 10
7.1.4 Geriatrics....................................................................................................... 10
8 ADVERSE REACTIONS ............................................................................................ 10
8.1 Adverse Reaction Overview .............................................................................. 10
8.2 Clinical Trial Adverse Reactions (Adults) ........................................................... 10
8.3 Less Common Clinical Trial Adverse Reactions (Adults) .................................... 12
8.4 Abnormal Laboratory Findings: Hematologic, Clinical Chemistry and Other Quantitative Data (Adults) ........................................................................................... 13
8.5 Clinical Trial Adverse Reactions (Pediatrics) ...................................................... 14
8.6 Less Common Clinical Trial Adverse Reactions (Pediatrics)............................... 14
8.7 Post-Market Adverse Reactions ........................................................................ 15
9 DRUG INTERACTIONS ............................................................................................. 15
9.1 Overview .......................................................................................................... 15
9.2 Drug-Drug Interactions ...................................................................................... 15
10 ACTION AND CLINICAL PHARMACOLOGY............................................................. 15
10.1 Mechanism of Action ..................................................................................... 15
10.2 Pharmacodynamics ....................................................................................... 15
10.3 Pharmacokinetics .......................................................................................... 16
11 STORAGE, STABILITY AND DISPOSAL................................................................... 17
12 SPECIAL HANDLING INSTRUCTIONS ..................................................................... 17
PART II: SCIENTIFIC INFORMATION................................................................................... 18
13 PHARMACEUTICAL INFORMATION ........................................................................ 18
14 CLINICAL TRIALS..................................................................................................... 19
14.1 Trial Design and Study Demographics ........................................................... 19
15 NON-CLINICAL TOXICOLOGY ................................................................................. 20
PATIENT MEDICATION INFORMATION............................................................................... 21
PART I: HEALTH PROFESSIONAL INFORMATION
1 INDICATIONS
Trecondyv® (treosulfan) is indicated in combination with fludarabine as part of conditioning treatment prior to allogeneic hematopoietic stem cell transplantation (alloHSCT)
- in adult patients with AML or MDS at increased risk for standard conditioning therapies,
- in pediatric patients older than 1 year old with AML or MDS
Administration of treosulfan should be supervised by a physician experienced in conditioning treatment followed by alloHSCT.
Limitations of Use
Trecondyv® is not indicated for patients undergoing allo HSCT for Fanconi anemia and other DNA breakage repair disorders.
1.1 Pediatrics
Pediatrics (> 1 year to 18 years): The use of Trecondyv® has not been fully investigated in the pediatric population.
1.2 Geriatrics
Geriatrics (> 65 years of age): Evidence from clinical studies and experience suggests that use of Trecondyv® in the geriatric population is not associated with significant differences in safety or effectiveness.
No dose adjustment is necessary in any subset of the elderly population.
2 CONTRAINDICATIONS
Treosulfan is contraindicated in patients who are hypersensitive to this drug or to any ingredient in the formulation, including any non-medicinal ingredient, or component of the container. For a complete listing, see Dosage Forms, Strengths, Composition and Packaging.
- Active non-controlled infectious disease
- Severe concomitant cardiac, lung, liver, and renal impairment
- Fanconi anemia and other DNA breakage repair disorders
- Pregnancy
- Administration of live vaccine
3 SERIOUS WARNINGS AND PRECAUTIONS BOX
4 DOSAGE AND ADMINISTRATION
4.1 Dosing Considerations
Administration of Trecondyv® should be supervised by a physician experienced in conditioning treatment followed by alloHSCT.
4.2 Recommended Dose and Dosage Adjustment
Trecondyv® is given in combination with fludarabine.
The recommended dose and schedule of administration is:
- Treosulfan 10 g/m² body surface area (BSA) per day as a two-hour intravenous infusion, given on three consecutive days (day -4, -3, -2) before stem cell infusion (day 0). The total treosulfan dose is 30 g/m²;
- Fludarabine 30 mg/m² BSA per day as a 0.5-hour intravenous infusion, given on five consecutive days (day -6, -5, -4, -3, -2) before stem cell infusion (day 0). The total fludarabine dose is 150 mg/m²;
- Treosulfan should be administered before fludarabine on days -4, -3, -2 (FT10 regimen).
Health Canada has not authorized the use of Trecondyv® in children less than 1 year of age.
No dose adjustment is necessary for mild or moderate liver or renal impairment, but treosulfan is contraindicated in patients with severe impairment (see section CONTRAINDICATION).
4.3 Administration
Trecondyv® is for intravenous use as a two-hour infusion. Intravenous administration should be performed using a safe technique to avoid extravasation.
When handling treosulfan, inhalation, skin contact or contact with mucous membranes should be avoided. Pregnant personnel should be excluded from handling cytotoxics.
Consider providing prophylactic anti-emetic therapy during Trecondyv® treatment.
4.4 Reconstitution
Dissolve Trecondyv® with 0.45% or 0.9% Sodium Chloride Injection or 5% Glucose Injection or Water for Injection.
Trecondyv® is dissolved in its original glass container by shaking with solvent. Reconstituted
Serious Warnings and Precautions:
- Myelosuppression
- Causes severe and prolonged myelosuppression.
- Hematopoietic stem cell transplantation is required to prevent potentially fatal complications of the prolonged myelosuppression
solutions of Trecondyv® may be combined into a larger glass vial, EVA bag or PE bag.
In case solubility issues are observed when shaking, prolonged standing time or slight warming of the reconstituted solution (hand warm) are useful to improve solubility.
Table 1 - Reconstitution
| Vial Size | Volume of Diluent to be Added to Vial | Approximate Vial Capacity | Nominal Concentration per mL |
|---|---|---|---|
| 1 g | 20 mL | 38 mL | 50 mg/mL |
| 5 g | 100 mL | 119 mL | 50 mg/mL |
The reconstituted solution of Trecondyv® is stable for 3 days if stored at 15°C to 30°C. Do not store under refrigeration (2°C - 8°C) as this might result in the formation of precipitate. Do not use if the solution contains a precipitate [see STORAGE, STABILITY AND DISPOSAL(11)]
In the absence of compatibility studies, treosulfan must not be mixed with other medicinal products.
4.5 Missed Dose
A missed dose would increase the risk for a primary graft failure.
5 OVERDOSAGE
| For management of a suspected drug overdose, contact your regional poison control centre. |
There is no known antidote to Trecondyv® other than hematopoietic stem cell transplantation. In the absence of hematopoietic stem cell transplantation, the recommended dose for Trecondyv® would constitute an overdose of treosulfan.
The principal toxic effect of treosulfan is profound myeloablation and pancytopenia. In addition, acidosis, skin toxicity, nausea, vomiting and gastritis may occur. The hematologic status should be closely monitored and vigorous supportive measures instituted as medically indicated.
6 DOSAGE FORMS, STRENGTHS, COMPOSITION AND PACKAGING
Table 2 – Dosage Forms, Strengths, Composition and Packaging.
Trecondyv® is supplied as a sterile, white crystalline, lyophilized powder in single use glass vials containing 1 g or 5 g treosulfan.
| Route of Administration | Dosage Form / Strength/Composition | Non-medicinal Ingredients |
| Intravenous infusion | Lyophilized powder 1 g or 5 g per vial | None |
Trecondyv® 1 g lyophilized powder
Colourless type I glass vial, with rubber stopper and aluminium cap containing 1 g of treosulfan.
Trecondyv® 5 g lyophilized powder
Colourless type I glass vial, with rubber stopper and aluminium cap containing 5 g of treosulfan.
Trecondyv® is available in cartons of 1 or 5 vials each.
7 WARNINGS AND PRECAUTIONS
Please see the Serious Warnings and Precautions Box at the beginning of Part I: Health Professional Information [Section 3].
The following warnings pertain to different physiologic effects of Trecondyv® in the setting of allo HSCT.
General
Treosulfan is considered an irritant. Intravenous application should be performed using a safe technique. If extravasation is suspected, general safety measures should be implemented. No specific measure has been proven to be recommendable.
During a phase 3 clinical trial (MC-FludT.14/L Trial II) treatment emergent adverse events (TEAEs) were reported by 92.6% of patients in the treosulfan treatment group. TEAEs were most commonly reported in the SOCs “Gastrointestinal disorders”, “General disorders and administration site conditions”, and “Musculoskeletal and connective tissue disorders” (TEAEs reported by 68.1%, 56.3%, and 37.8% of patients, respectively).
TEAEs of at least CTCAE Grade III were reported by 54.8% of patients in the treosulfan treatment group. Severe Adverse Events (SAEs) were reported by 8.5% of patients in the treosulfan treatment group.
Carcinogenesis and Mutagenesis
Secondary malignancies are well-established complications in long-term survivors after alloHSCT.
The possible risk of a second malignancy should be explained to the patient. On the basis of human data, treosulfan has been classified by the International Agency for Research on Cancer (IARC) as a human carcinogen Group 1.
Cardiovascular
Patients with severe cardiac impairment diagnosed by ECG and left ventricular ejection fraction (LVEF) < 40% or with severe pulmonary impairment were excluded from the pivotal clinical study and therefore the safety and efficacy of TRECONDYV in these patients have not been established.
During the clinical program of treosulfan cardiac arrhythmias (e.g. atrial fibrillation, sinus arrhythmia) and cardiac failure occurred in 18.1% and 1.0% of the adult patients treated with treosulfan-based conditioning regimen, respectively. The treatment emergent serious cardiac adverse events - left ventricular systolic dysfunction, myocardial infarction, paroxysmal atrial tachycardia and right ventricular dysfunction - were reported in the treosulfan treatment group during a phase 3 clinical trial (MC-FludT.14/L Trial II), although none was considered related to treosulfan.
No thorough clinical QT/QTc study was performed to rule out the effect of TRECONDYV on in vivo QT prolongation. In vitro studies on electrophysiological activity of treosulfan on key cardiac ion channels and tests of proarrhythmic potential in human induced pluripotent stem cell (iPS) derived cardiomyocytes, using a microelectrode array (MEA) assay, did not reveal dose-limiting functional or structural changes.
Driving and Operating Machinery
Treosulfan has moderate influence on the ability to drive and use machines. It is likely that certain adverse reactions of treosulfan like nausea, vomiting or dizziness could affect these functions.
Due caution should be exercised when driving or operating a vehicle or potentially dangerous machinery.
Gastrointestinal
Oral mucositis (including high-grade severity) is a very common undesirable effect of treosulfan-based conditioning followed by alloHSCT (8). Use of mucositis prophylaxis (e.g. topical antimicrobials, barrier protectants, ice and adequate oral hygiene) is recommended.
Graft vs Host Diseases
Graft vs. Host Disease (GvHD) is commonly observed in patients treated with an allogeneic HSCT. Respective results obtained with 10 g/m²/d x 3 regimen are shown in the following table.
Table 3: Summary of Graft vs Host Disease observed in an active-controlled trial (MC-FludT.14/L Trial II)
| Parameter | Treosulfan | Busulfan | P value |
| Number of patients | 268 | 283 | |
| Acute GvHD, all Grades; % (95% CI) | 52.8 (46.8, 58.8) | 57.2 (51.5, 63.0) | 0.2038 |
| Acute GvHD, Grades III/IV; % (95% CI) | 6.4 (3.4, 9.3) | 8.1 (4.9, 11.3) | 0.4267 |
| Chronic GvHDa; % (95% CI) | 61.7 (55.1, 68.3) | 60.3 (53.8, 66.7) | 0.9964 |
| Extensive chronic GvHD; % (95% CI) | 19.8 (14.5, 25.1) | 28.6 (22.5, 34.7) | 0.0750 |
Hepatic
Transaminases, bilirubin, gamma-glutamyl transferase and alkaline phosphatase are commonly increased in patients treated with treosulfan-based conditioning.
Hematologic
Profound myelosuppression with pancytopenia is the desired therapeutic effect of treosulfan-based conditioning treatment, occurring in all patients. It is therefore recommended to monitor blood cell counts frequently until recovery of the hematopoietic system. During phases of severe neutropenia (median duration of neutropenic period is 14-17.5 days in adults and 21-24 days in pediatric patients as observed in study MC-FludT.17/M) the risk of infection is increased.
Prophylactic or empiric anti-infective treatment (bacterial, viral, fungal) should therefore be considered. Growth factors (G-CSF, GM-CSF), platelet and/or red blood cell support should be given as indicated.
Monitoring and Laboratory Tests (see also section 8.4)
Patients receiving TRECONDYV should be monitored daily with a complete blood count, including differential count and quantitative platelet count, until engraftment has been demonstrated.
To detect hepatotoxicity, serum transaminases, alkaline phosphatase, and bilirubin should be evaluated daily through transplant day 28.
Cardiac function should be monitored regularly in patients receiving TRECONDYV.
Neurologic
During the clinical program of treosulfan, headache and dizziness occurred in 24.5% and 9.0% of the adult patients treated with treosulfan-based conditioning regimen, respectively. The treatment emergent serious neurologic adverse events - intracranial hemorrhage and syncope - were reported in the treosulfan treatment group during a phase 3 clinical trial (MC-FludT.14/L Trial II). In only one patient, who experienced encephalitis infection and intracranial hemorrhage as a complication of sepsis, the event was considered related to treosulfan.
Respiratory
During the clinical program of treosulfan epistaxis and dyspnea occurred in 10.3% and 8.6% of the adult patients treated with treosulfan-based conditioning regimen, respectively. The treatment emergent serious respiratory adverse events – respiratory failure, bronchopulmonary hemorrhage and lung infection - were reported in the treosulfan treatment group during a phase 3 clinical trial (MC-FludT.14/L Trial II). Only lung infection was considered related to treosulfan.
There was a significant association between age and respiratory toxicity in pediatric patients treated with treosulfan-based conditioning.
Sexual Health
Reproduction
Both sexually active men and women of childbearing potential have to use effective contraception during and up to 6 months after treatment.
Function
Ovarian suppression and amenorrhea with menopausal symptoms commonly occur in pre-menopausal patients.
Fertility
Treosulfan can impair fertility. Therefore, men treated with treosulfan are advised not to father a child during and up to 6 months after treatment and to seek advice on cryo-conservation of sperm prior to treatment because of the possibility of irreversible infertility due to therapy with treosulfan.
Skin
An increase of skin disorders (e.g. rash, dermatitis) was observed when patients received sodium bicarbonate-containing hydration in the course of treosulfan infusion because this might accelerate the pH-dependent formation of alkylating epoxides [see Mechanism of Action (10.1)].
On the days of chemotherapy, skin cream should be omitted.
Dermatitis diaper may occur in small children because of excretion of treosulfan in the urine.
Therefore, diapers should be changed frequently during the 6–8 hours after each infusion of treosulfan.
7.1 Special Populations
7.1.1 Pregnant Women
There is no experience from the use of treosulfan in pregnant women. Treosulfan is contraindicated during pregnancy [see CONTRAINDICATIONS (2)].
7.1.2 Breast-feeding
It is unknown if the drug is excreted in human milk. Because many drugs are excreted in human milk precaution should be exercised.
Breast-feeding should be discontinued during treatment with treosulfan.
7.1.3 Pediatrics
Pediatrics (> 1 year to 18 years): The use of Trecondyv® has not been fully investigated in the pediatric population.
7.1.4 Geriatrics
Eighty-one (13.2%) of the 613 adult patients treated within the clinical trial program for Trecondyv® were above the age of 65 years.
8 ADVERSE REACTIONS
8.1 Adverse Reaction Overview
Profound myelosuppression/pancytopenia is the desired therapeutic effect of conditioning therapy and occurs in all patients. Blood cell counts usually recover after HSCT.
The most common (> 10%) adverse reactions observed in 5 clinical studies in 613 adults with treosulfan-based conditioning followed by alloHSCT include gastrointestinal disorders (nausea 38.5%, stomatitis 36.4%, vomiting 22.5%, diarrhea 15.2%), increases of bilirubin 17.9%, fatigue 14.8%, infections 12.9%, and febrile neutropenia 10.9%.
The most common (> 10%) adverse reactions observed in two clinical studies in 115 pediatric patients with treosulfan-based conditioning followed by alloHSCT include gastrointestinal disorders (stomatitis 67.0%, vomiting 41.7%, diarrhea 34.8%, nausea 27.8%, abdominal pain 17.4%), hepatotoxicity 26.1%, pyrexia 13.0%, infections 12.2%, increased alanine aminotransferase 11.3%, alopecia 10.4%, and pruritus 10.4%.
8.2 Clinical Trial Adverse Reactions (Adults)
Because clinical trials are conducted under very specific conditions, the adverse reaction rates observed in the clinical trials may not reflect the rates observed in practice and should not be compared to the rates in the clinical trials of another drug. Adverse reaction information from clinical trials is useful for identifying drug-related adverse events and for approximating rates.
The frequencies of adverse reactions reported in the table below are derived from a large active-controlled phase III clinical trial (MC-FludT.14/L Trial II) in a total of 551 adult patients where a conditioning regimen of treosulfan plus fludarabine was compared to a reduced intensity conditioning regimen consisting of busulfan plus fludarabine (NCT00822393). Median age of patients in the whole group was 60 years (range 31-70); 61% of patients were male; the underlying diseases were acute myeloid leukemia (64%) and myelodysplastic syndromes (36%).
Treosulfan was administered at a dose of 10 g/m² BSA on 3 consecutive days; Busulfan was administered at a dose of 3.2 mg/kg on 2 consecutive days. Fludarabine was added in both groups at a dose of 30 mg/m² on 5 consecutive days.
| Table 3: Summary of the Incidence (occurring in ≥ 5% of Treated Patients) of Non-Hematologic Treatment Emergent Adverse Events by System Organ Class and Preferred Term (MedDRA 20.0) in an active-controlled trial (MC-FludT.14/L Trial II) |
| Nonhematological Treatment Emergent Adverse Events (TEAEs) | Percent Incidence | |||||||||||
|---|---|---|---|---|---|---|---|---|---|---|---|---|
| TEAEs all grades | TEAEs grade III/IV | |||||||||||
| Treatment group | Treosulfan n = 270 | Busulfan n = 283 | Treosulfan n = 270 | Busulfan n = 283 | ||||||||
| Infections and infestations | ||||||||||||
| Infections | 27.0 | 23.7 | 15.2 | 9.2 | ||||||||
| Immune system disorders | ||||||||||||
| Allergic reaction | 5.6 | 7.8 | 0.4 | 0.4 | ||||||||
| Metabolism and nutrition disorders | ||||||||||||
| Anorexia | 8.9 | 9.2 | 1.9 | 1.4 | ||||||||
| Hypomagnesemia | 5.2 | 2.8 | 0 | 0 | ||||||||
| Nervous system disorders | ||||||||||||
| Headache | 16.3 | 18.4 | 1.1 | 0.7 | ||||||||
| Dizziness | 6.3 | 4.9 | 0 | 0.4 | ||||||||
| Ear and labyrinth disorders | ||||||||||||
| Vertigo | 4.4 | 8.5 | 0 | 0.7 | ||||||||
| Vascular disorders | ||||||||||||
| Hypertension | 14.1 | 21.2 | 7.8 | 9.5 | ||||||||
| Hypotension | 7.0 | 4.2 | 1.9 | 1.8 | ||||||||
| Respiratory, thoracic and mediastinal disorders | ||||||||||||
| Epistaxis | 6.7 | 7.8 | 0 | 0.7 | ||||||||
| Dyspnea | 5.2 | 7.8 | 0.7 | 1.4 | ||||||||
| Gastrointestinal disorders | ||||||||||||
| Mucositis oral (stomatitis) | 37.8 | 47.7 | 5.9 | 7.4 | ||||||||
| Nausea | 33.0 | 41.0 | 3.0 | 6.0 | ||||||||
| Nonhematological Treatment Emergent Adverse Events (TEAEs) | Percent Incidence |
|---|
| TEAEs all grades | TEAEs grade III/IV |
|---|
| Treatment group | Treosulfan n = 270 | Busulfan n = 283 | Treosulfan n = 270 | Busulfan n = 283 |
|---|---|---|---|---|
| Vomiting | 21.9 | 19.4 | 0.7 | 1.4 |
| Diarrhea | 15.9 | 18.4 | 1.5 | 1.4 |
| Constipation | 12.2 | 11.7 | 0.4 | 0 |
| Abdominal pain | 10.7 | 9.9 | 1.5 | 0.7 |
| Skin and subcutaneous tissue disorders | ||||
| Rash maculo-papular | 11.9 | 8.8 | 1.1 | 1.4 |
| Pruritus | 5.9 | 4.2 | 0.4 | 0 |
| Purpura | 5.2 | 3.5 | 0 | 0 |
| Musculoskeletal and connective tissue disorders | ||||
| Back pain | 14.8 | 13.1 | 2.6 | 0.4 |
| Bone pain | 13.7 | 9.9 | 0.7 | 0.7 |
| Arthralgia | 10.0 | 3.5 | 0.7 | 0.4 |
| Pain in extremity | 8.5 | 3.9 | 0.7 | 1.1 |
| General disorders and administration site conditions | ||||
| Fatigue | 12.2 | 12.4 | 1.1 | 0 |
| Fever | 34.4 | 35.7 | 0.7 | 3.2 |
| Edema limbs | 22.6 | 13.4 | 0.4 | 1.4 |
| Chills | 7.4 | 5.7 | 0.4 | 0 |
| Localized edema | 5.9 | 4.9 | 0.4 | 0 |
| Pain | 5.9 | 2.8 | 0.4 | 0 |
| Investigations | ||||
| Alanine transaminase (ALT) increased | 8.5 | 6.4 | 5.2 | 3.2 |
| Aspartate transaminase (AST) increased | 8.5 | 4.9 | 4.4 | 2.5 |
| Bilirubin increased | 9.3 | 6.4 | 3.3 | 2.8 |
| Gamma-glutamyltransferase (γGT) increased | 7.4 | 12.0 | 4.4 | 8.8 |
| Weight gain | 7.0 | 6.4 | 0 | 0 |
8.3 Less Common Clinical Trial Adverse Reactions (Adults)
Additional Adverse Reactions observed with treosulfan-based conditioning followed by alloHSCT in 5 clinical trials in adult patients by System Organ Class and Preferred Term.
Blood and lymphatic system disorders: Febrile neutropenia
Cardiac disorders: Cardiac arrhythmias (e.g. atrial fibrillation, sinus arrhythmia), cardiac arrest, cardiac failure, myocardial infarction, pericardial effusion
Eye disorders: Dry eye
Gastrointestinal disorders: Oral pain, gastritis, dyspepsia, dysphagia, gastrointestinal hemorrhage, mouth hemorrhage, abdominal distension, esophageal or gastrointestinal pain, dry mouth, neutropenic colitis, esophagitis, anal inflammation, mouth ulceration
General disorders and administration site conditions: Edema, non-cardiac chest pain, injection site reaction, feeling cold
Hepatobiliary disorders: Veno-occlusive liver disease, hepatotoxicity, hepatic failure, hepatomegaly, hepatic pain
Immune system disorders: Hypersensitivity
Infections and infestations: Sepsis, septic shock
Investigations: Alkaline phosphatase increased, C reactive protein increased, weight decreased, blood creatinine increased, blood lactate dehydrogenase increased
Metabolism and nutrition disorders: Hyperglycemia, acidosis, impaired glucose tolerance, electrolyte imbalance
Musculoskeletal and connective tissue disorders: Myalgia, muscular weakness
Neoplasms benign, malignant and unspecified (including cysts and polyps): Treatment related second malignancy
Nervous system disorders: Peripheral sensory neuropathy, intracranial hemorrhage, encephalopathy, extrapyramidal disorder, syncope, paresthesia
Psychiatric disorders: Insomnia, confusional state, agitation
Renal and urinary disorders: Acute kidney injury, hematuria, urinary tract pain, renal failure, hemorrhagic cystitis, dysuria
Respiratory, thoracic and mediastinal disorders: Pneumonitis, pleural effusion, pharyngeal or laryngeal inflammation, cough, laryngeal or oropharyngeal pain, hiccups, hypoxia, dysphonia
Skin and subcutaneous tissue disorders: Erythema, palmar plantar erythrodysesthesia syndrome, alopecia, erythema multiforme, dermatitis acneiform, rash, hyperhidrosis, dry skin, generalized erythema, dermatitis, skin necrosis or ulcer, skin hyperpigmentation
Vascular disorders: Flushing, hematoma, embolism, hemorrhage
8.4 Abnormal Laboratory Findings: Hematologic, Clinical Chemistry and Other Quantitative Data (Adults)
Hematologic
Significant suppression of the patient’s blood cell counts is a typical epiphenomenon of alloHSCT which occurs in all patients. To reduce the occurrence of cytopenia-caused side effects (anemia: fatigue etc., leukopenia: infections; thrombocytopenia: bleeding), patients usually receive blood transfusions during the critical aplastic phase between HSCT and the next 4 weeks.
Table 4: Duration of cytopenias in adult patients treated with the FT10 regimen
| Duration (days) | Neutropenia | Leukocytopenia | Thrombocytopenia | ||||||||||
| < 0.5 × 10⁹/L | < 1 × 10⁹/L | < 20 × 109/L | < 50 × 109/L | ||||||||||
| Median | 14 | 14 | 13 | 15 | |||||||||
| 25%/75% percentiles | 12 / 21 | 11 / 18 | 0 / 38 | 10 / 84 | |||||||||
Clinical chemistry
A significant proportion of patients had already laboratory liver parameters above the upper limit of normal (ULN) at baseline.
Table 5: Percent of 613 adult patients with laboratory values above ULN; n (% of patients)
| Time point | Laboratory parameter | ||||||||||||
| AST | ALT | γGT | AP | Bilirubin | |||||||||
| Baseline | 95 (15.6%) | 165 (27.0%) | 202 (33.4%) | 73 (12.2%) | 38 (6.2%) | ||||||||
| Day -3 | 141 (24.9%) | 189 (32.4%) | 276 (48.3%) | 57 (10.2%) | 144 (24.6%) | ||||||||
| Day -1 | 86 (14.8%) | 183 (30.9%) | 284 (49.0%) | 42 (7.4%) | 188 (31.6%) | ||||||||
| Day +6 | 168 (28.4%) | 336 (56.2%) | 357 (61.0%) | 56 (9.8%) | 243 (40.5%) | ||||||||
| Day +14 | 34 (5.8%) | 125 (20.9%) | 346 (59.2%) | 122 (21.4%) | 173 (29.0%) | ||||||||
| Day +28 | 96 (16.7%) | 157 (26.7%) | 307 (54.1%) | 116 (20.5%) | 108 (18.5%) | ||||||||
| AST = aspartate transaminase; ALT = alanine transaminase; γGT = gamma-glutamyltransferase; AP = alkaline phosphatase | |||||||||||||
Mean creatinine values were in normal range and did not much change during treatment with treosulfan-based conditioning.
8.5 Clinical Trial Adverse Reactions (Pediatrics)
Safety of treosulfan (10-14 g/m² on 3 consecutive days) combined with fludarabine (and mostly with thiotepa) was evaluated in two clinical trials in pediatric patients that included 70 patients with malignant diseases (AML, MDS, acute lymphoblastic leukemia [ALL], juvenile myelomonocytic leukemia [JMML]) and 45 patients with various non-malignant diseases.
Compared to adult patients, the following differences were observed. Gastrointestinal disorders (75.7% vs. 62.5%) and hepatobiliary disorders (27.8% vs. 1.8%) were more frequently observed in pediatric patients. The median (25%/75% percentiles) duration of neutropenia was 22 (17 / 26) days in pediatric patients with malignant diseases and 20 (16 / 26) days in patients with non-malignant disorders and therefore significantly longer than in adult patients (14 [12 / 21] days). However, the overall incidence of infections in 115 pediatric patients was 12.2% and thus comparable to that seen in adults.
8.6 Less Common Clinical Trial Adverse Reactions (Pediatrics)
Additional Adverse Reactions observed with treosulfan-based conditioning followed by alloHSCT in 2 clinical trials in pediatric patients by System Organ Class and Preferred Term.
Blood and lymphatic system disorders: Febrile neutropenia
Eye disorders: Conjunctival hemorrhage, dry eye
Gastrointestinal disorders: Dysphagia, oral pain, neutropenic colitis, anal inflammation, dyspepsia, proctitis, gastrointestinal pain, constipation
General disorders and administration site conditions: Chills, fatigue, pain
Hepatobiliary disorders: Veno-occlusive liver disease, hepatomegaly
Investigations: Aspartate aminotransferase increased, bilirubin increased, gamma-glutamyltransferase increased
Metabolism and nutrition disorders: Alkalosis, electrolyte imbalance, hypomagnesemia
Musculoskeletal and connective tissue disorders: Pain in extremities
Neoplasms benign, malignant and unspecified (including cysts and polyps): Treatment related second malignancy
Nervous system disorders: Headache, paresthesia, seizure
Psychiatric disorders: Insomnia, confusional state, agitation
Renal and urinary disorders: Acute kidney injury, renal failure, noninfective cystitis
Reproductive system and breast disorders: Scrotal erythema
Respiratory, thoracic and mediastinal disorders: Oropharyngeal pain, epistaxis, hypoxia
Skin and subcutaneous tissue disorders: Dermatitis exfoliative, maculopapular rash, rash, erythema, pain of skin, skin hyperpigmentation, skin ulcer, erythema multiforme, urticaria, dermatitis bullous, dermatitis acneiform, palmar plantar erythrodysesthesia syndrome, dermatitis diaper
Vascular disorders: Capillary leak syndrome, hypertension, hypotension
8.7 Post-Market Adverse Reactions
A report from an investigator-initiated trial performed in children with primary immunodeficiencies listed four cases of seizures occurring after a conditioning regimen with treosulfan.
9 DRUG INTERACTIONS
9.1 Overview
Drug interactions with treosulfan were not studied in vivo. Detailed in vitro studies did not completely exclude potential interactions between high plasma concentrations of treosulfan and CYP3A4, CYP2C19, or P-gp substrates.
Physiologically-based pharmacokinetic (PBPK) modeling with the sensitive index substrates midazolam, omeprazole, and digoxin for CYP3A4, CYP2C19, and P-gp predicted a weak interaction (AUCratio ≥ 1.25 and < 2) for CYP3A4, and CYP2C19, and a negligible (AUCratio < 1.25) interaction for P-gp. Therefore, medicinal products with a narrow therapeutic index that are substrates for CYP3A4 or CYP2C19 should not be given during treatment with treosulfan.
9.2 Drug-Drug Interactions
Interactions with other drugs have not been established.
10 ACTION AND CLINICAL PHARMACOLOGY
10.1 Mechanism of Action
Treosulfan is a prodrug of a bifunctional alkylating agent with cytotoxic activity to hematopoietic stem cells. The activity of treosulfan is due to the spontaneous, pH-dependent conversion into a mono-epoxide intermediate and di-epoxybutan.
These epoxides alkylate and cross-link nucleophilic centers of deoxyribonucleic acid (DNA) and other biological molecules involved in various physiological functions and are considered responsible for the stem cell depleting, immune-suppressive and antineoplastic effects.
10.2 Pharmacodynamics
Treosulfan has a broad antineoplastic and antileukemic activity. This was demonstrated against transplanted mouse and rat lymphomas/leukemias, sarcomas and hepatomas, human tumor xenografts, human tumor biopsies and cell lines.
The immunosuppressive effects of treosulfan are attributed to its toxicity against primitive and committed hematopoietic progenitor cells, T and NK cells, reduction of cellularity of primary and secondary lymphatic organs and a preclusive effect on the ‘cytokine storm’ that precedes the development of Graft-versus-Host-Disease (GvHD) and is involved in the pathogenesis of hepatic sinusoidal-obstruction syndrome (HSOS). Due to the high engraftment rates after administration of the recommended Trecondyv® doses no clear dose-response relationship with regard to engraftment or time to engraftment after alloHSCT was described.
10.3 Pharmacokinetics
The pharmacokinetics of Trecondyv® was studied in 24 adult patients participating in a prospective trial of a treosulfan-fludarabine conditioning regimen prior to alloHSCT. Patients received 14 g/m²/day treosulfan intravenously for 3 consecutive days.
With a terminal half-life close to 2 hours and no quantifiable pre-dose concentrations on the second and third day of treatment, there was no evidence of Trecondyv® accumulation in plasma after multiple dosing. Median values of all pharmacokinetic parameters were quite comparable for the first and third administration. Further pharmacokinetic parameters are available from the literature for dose levels ranging from 8 to 14 g/m² treosulfan infused over 2 hours.
Table 6: Summary of Treosulfan’s Pharmacokinetic Parameters in Adult Patients (Arithmetic means ± standard deviation)
TREO dose g/m² | n | Cmax mcg/mL | AUC0-∞ mcg/mL × h | Half-life h | CLtot mL/min | Vss L | Reference |
|---|---|---|---|---|---|---|---|
| 8 | 4 | 181 ± 36 | 541 ± 107 | 1.75 ± 0.06 | 255 ± 59 | 30 ± 8 | Hilger et al. |
| 10 | 3 | 306 ± 94 | 940 ± 293 | 1.99 ± 0.61 | 190 ± 63 | 26 ± 12 | |
| 12 | 8 | 260 ± 35 | 898 ± 104 | 2.1 ± 0.5 | 225 ± 23 | 34 ± 5 | Beelen et al. |
| 14 | 10 | 322 ± 47 | 1104 ± 173 | 2.0 ± 0.6 | 216 ± 32 | 31 ± 7 | |
| 12 | 4 | 461 ± 102 | 1365 ± 293 | 1.73 ± 0.10 | 154 ± 35 | 16.9 ± 4.3 | Nemecek et al. |
| 14 | 12 | 409 ± 84 | 1309 ± 262 | 1.83 ± 0.30 | 185 ± 37 | 22.1 ± 3.8 | |
| 14 | 24 | 471 ± 87 | 1462 ± 261 | 1.84 ± 0.30 | 298 ± 63 | 46.9 ±9.0 | MC-FludT.14/L Trial I |
| Cmax = maximum plasma concentration; AUC0-∞ = Area under the concentration versus time curve from time point zero up to infinity; CLtot = total clearance; Vss = volume of distribution at steady state | |||||||
References:
Hilger RA et al. Clinical pharmacokinetics of intravenous treosulfan in patients with advanced solid tumors. Cancer Chemother Pharmacol. 1998; 42: 99-104
Beelen DW et al. Dose-escalated treosulphan in combination with cyclophosphamide as a new preparative regimen for allogeneic haematopoietic stem cell transplantation in patients with an increased risk for regimen-related complications. Bone Marrow Transplant. 2005; 35(3):233-41
Nemecek ER et al. Conditioning with treosulfan and fludarabine followed by allogeneic hematopoietic cell transplantation for high-risk hematologic malignancies. Biol Blood Marrow Transplant. 2011 Mar; 17(3):341-50
Absorption: After intravenous administration, peak plasma levels are reached at the end of the infusion time. Maximum plasma levels (mean ± SD) in adult patients after a 2-hour intravenous infusion are provided in Table 6.
Distribution: Treosulfan is rapidly distributed in the body; however, its penetration through the blood-brain-barrier is quite limited [see Nonclinical Toxicology (16)]. The volume of distribution in adult patients is about 20–47 liters. No dose accumulation with the recommended daily treatment on three consecutive days was observed.
A microscale thermophoresis method demonstrated that treosulfan does not bind to human serum albumin.
Metabolism: Under physiological conditions (pH 7.4, temperature 37 °C), the pharmacologically inactive treosulfan is converted spontaneously (non-enzymatically) into the active monoepoxide intermediate (2S,3S)-1,2-epoxybutane-3,4-diol-4-methanesulfonate) and finally to L-diepoxibutane (2S,3S)-1,2:3,4-diepoxybutane).
Elimination: Plasma concentrations of treosulfan decline exponentially and are best described by a first order elimination process fitted by a two-compartment model.
The terminal half-life (T1/2ß) of intravenously administered treosulfan is approximately 2 hours. Approximately14–40% of the treosulfan dose is excreted unchanged with the urine within 24 hours.
Special Populations and Conditions
Pediatrics (> 1 year to 18 years): The use of Trecondyv® has not been fully investigated in the pediatric population.
Geriatrics: Between patients < 50 years and ≥ 50 years of age, only small differences in the pharmacokinetic parameters were observed.
Sex: Median values of Cmax, AUC, half-life, total clearance and volume of distribution were quite comparable in male and female patients.
Hepatic Insufficiency: No pharmacokinetic studies with treosulfan were conducted in patients with severe hepatic impairment, because such patients are generally excluded from alloHSCT.
Renal Insufficiency: No pharmacokinetic studies with treosulfan were conducted in patients with severe renal impairment, because such patients are generally excluded from alloHSCT. About14–40% of treosulfan is excreted in urine; however, an influence of renal function on overall clearance of treosulfan was not observed.
11 STORAGE, STABILITY AND DISPOSAL
Unopened vials of Trecondyv® should be stored at room temperature 15°C to 30°C.
Trecondyv® dissolved in 0.45% or 0.9% Sodium Chloride Injection or 5% Glucose Injection or Water for Injection is stable for 3 days if stored at 15°C to 30°C.
Do not store under refrigeration (2°C -8°C) as this might result in the formation of precipitate. Do not use if the solution contains a precipitate.
12 SPECIAL HANDLING INSTRUCTIONS
Trecondyv® is a cytotoxic drug. Follow applicable special handling and disposal procedures.
PART II: SCIENTIFIC INFORMATION
13 PHARMACEUTICAL INFORMATION
Drug Substance
Common name: treosulfan
Chemical name: (2S,3S)-2,3-dihydroxy-4-(methanesulfonyloxy)butyl methanesulfonate
Molecular formula and molecular mass: C6H14O8S2; 278.3 g/mol
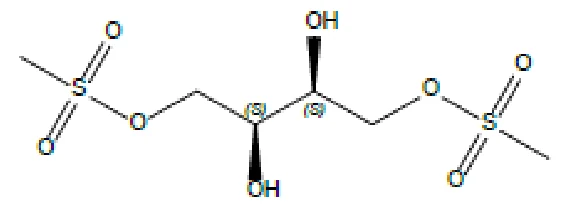
Structural formula:
Physicochemical properties:
Physical description: White crystalline powder
pKa: 12.84
Solubility (25 °C): 13 % (m/v) in acetone; 7 % (m/v) in water; 1 % (m/v) in ethanol 96%;
0.05 % (m/v) in chloroform
Solubility of Treosulfan in water at pH 1 to pH 8 at 37°C is from 150 to 200 mg/mL.
14 CLINICAL TRIALS
14.1 Trial Design and Study Demographics
Table 7 - Summary of patient demographics for clinical trials in alloHSCT
| Study | Trial design | Dosage, route of administration and duration | Study subjects (n) | Mean age (Range) | Sex (male/female) | ||
|---|---|---|---|---|---|---|---|
| MC-FludT.14/L Trial I | Randomized, active controlled, parallel-group, open label, group-sequential phase III trial in adult patients w ith AML or MDS | Treosulfan arm: 14 g/m²/d IV infusion (2 hours) Day –6 to –4 before HSCT (day 0) | 168 | 57.3 (21-70) years | 76 / 92 | ||
Control arm FB 3.2 mg/kg/d IV infusion (2 hours) Day –4 to –3 before HSCT (day 0) | 152 | 57.8 (24-70) years | 85 / 67 | ||||
| MC-FludT.14/L Trial II | Randomized, active controlled, parallel-group, open label, group-sequential phase III trial in adult patients w ith AML or MDS | Treosulfan arm: 10 g/m²/d IV infusion (2 hours) Day –4 to –2 before HSCT (day 0) | 270 | 59.3 (37-70) years | 163 / 107 | ||
Control arm FB 3.2 mg/kg/d IV infusion (2 hours) Day –4 to –3 before HSCT (day 0) | 283 | 59.9 (31-70) years | 173 / 110 | ||||
| FB = Fludarabine plus busulfan | |||||||
MC-FludT.14/L consists of two separate active-controlled trials which differ in the treosulfan regimens used. Both trials compared treosulfan/ fludarabine with a reduced intensity conditioning (RIC) regimen of busulfan/fludarabine (FB2) in elderly and/or comorbid patients with AML or MDS who are not eligible for a standard MAC regimen. In the first trial, a treosulfan dose of 14 g/m²/d × 3 (FT14 regimen) was used. An interim analysis after inclusion of 330 patients showed a slightly higher incidence of transplant-related mortality (TRM) in the experimental arm, mainly due to an increased rate of infections because of a significantly prolonged duration of neutropenia compared to the RIC regimen FB2. To reduce the duration of neutropenia, the dose of treosulfan was reduced from 14 to 10 g/m²/d × 3 and the timing of treosulfan administration shifted from days -6/-5/-4 to -4/-3/-2 in the subsequent Trial II (FT10 regimen). Trial II is considered as the pivotal study because the dose regimen used is the final dose regimen that is proposed for adult patients with malignant diseases (see 4.2). The final study report of this trial is based on 570 patients.
Study Results
Event-free survival (EFS) at 2 years was the primary endpoint of the pivotal study 14/L Trial II. Superiority of the treosulfan regimen versus busulfan could be demonstrated. Analyses of EFS at 2 years for various pre-defined subgroups (donor type, risk group, disease, age group, HCT-CI score, remission status at study entry, and various combinations of these parameters) were always in favor of the treosulfan regimen (hazard ratio [HR] of FT10 vs. FB2 < 1), with only one exception (risk group II of MRD patients; HR 1.18 [95% CI 0.61, 2.26]).
Results of the primary and further secondary endpoints are summarized in Table 8.
Table 8 - Results of study 14/L Trial II in patients with AML or MDS at 2 years (Full analysis set)
| Parameter | Treosulfan group % (95% CI) | Busulfan group % (95% CI) | Hazard ratio (95% CI) | P value | |||||
| Number of patients | 268 | 283 | |||||||
| Event-free survivala | 65.7 (59.5, 71.2) | 51.2 (45.0, 57.0) | 0.64 (0.49, 0.84)b | 0.00058b,d | |||||
| Overall survivala | 72.7 (66.8, 77.8) | 60.2 (54.0, 65.8) | 0.64 (0.48, 0.87)b | 0.0037b | |||||
| Cumulative incidence of non-relapse mortality | 12.0 (8.0, 15.9) | 20.4 (15.5, 25.2) | 0.63 (0.41, 0.97)c | 0.0343c | |||||
| Cumulative incidence of relapse/progression | 22.0 (16.9, 27.1) | 25.2 (20.0, 30.3) | 0.82 (0.59, 1.16)c | 0.2631c | |||||
| a Based on Kaplan-Meier estimates; b adjusted for donor type, risk group and center using Cox regression model; c adjusted for donor type as factor and risk group as stratum using Fine and Gray model; d P value for testing superiority | |||||||||
Pediatric studies
In pediatric patients, a conditioning regimen consisting of 10, 12 or 14 g/m²/d × 3 treosulfan (Day -6/-5/-4) plus fludarabine (30 mg/m²/d, Day -7 to -3) has been conducted. Safety and efficacy based on this study could not be established.
15 NON-CLINICAL TOXICOLOGY
Four week subchronic, intravenous treatment of rats with 10, 50 or 150 mg treosulfan/kg b.w./day (human equivalent dose [HED]: 1.6, 8.1, or 24.3 mg/kg b.w./day) resulted in hematologic changes, decreased relative spleen and thymus weights in the context of a lymphoid atrophy and bone marrow depression. Lymphohistiocytic infiltration in the skeletal musculature and signs of hematuria, preferentially in male animals, were observed. The no-observed-effect-level (NOEL) was below 10 mg /kg b.w./day. A linear dose-related systemic exposure of the animals to treosulfan and treosulfan monoepoxide was evident, without accumulation or sex-specific differences. Single intravenous administrations of 500 mg/kg b.w. treosulfan (HED: 81 mg/kg b.w.) to juvenile (PND 10) and young adult (PND 34 – 35) rats revealed a very low penetration of blood brain barrier by treosulfan. The treosulfan concentrations in brain tissue were 95% – 98% lower than in plasma. However, an approximately 3 fold higher exposure was found in the brain tissue of juvenile rats in comparison to young adults.
Subchronic treatment of juvenile rats from postnatal day 10 to 35 with daily doses of 10, 50 or 100 mg/kg b.w. treosulfan (human equivalent dose (HED): 1.6, 8.1, 16.2 mg/kg b.w.) resulted in completely reversible hematological changes in all dose groups. A slightly delayed physical development indicated by decreased body weight, reduced relative organs weights, and a slightly delayed time point of vaginal opening were noted in the high-dosed rats.