


Product Monograph - Varilrix
Recent Major Label Changes
| 2026-02 |
|---|---|
| 2026-02 |
| 2026-02 |
| 2026-02 |
Table of Contents
Certain sections or subsections that are not applicable at the time of the preparation of the most recent authorized product monograph are not listed.
Recent Major Label Changes ................................................................................................... 2
Table of Contents ................................................................................................................... 2
Part 1: Healthcare Professional Information ........................................................................... 4
- 1.
Indications ....................................................................................................................... 4
1.1. Pediatrics .................................................................................................................. 4
1.2. Geriatrics .................................................................................................................. 4
- 2. Contraindications ............................................................................................................ 4
- 4.
Dosage and Administration ............................................................................................. 5
4.2. Recommended Dose and Dosage Adjustment ............................................................... 5
4.3. Reconstitution ............................................................................................................... 5
4.4. Administration ............................................................................................................... 7
- 5. Overdose ......................................................................................................................... 7
- 6. Dosage Forms, Strengths, Composition, and Packaging ................................................... 7
- 7.
Warnings and Precautions ............................................................................................... 8
General ................................................................................................................................. 8
Immune .............................................................................................................................. 10
7.1. Special Populations ................................................................................................ 10
7.1.1. Pregnancy ...................................................................................................... 10
7.1.2. Breastfeeding ................................................................................................ 10
7.1.3. Pediatrics ....................................................................................................... 10
- 8.
Adverse Reactions ......................................................................................................... 10
8.1. Adverse Reaction Overview .................................................................................... 10
8.2. Clinical Trial Adverse Reactions .............................................................................. 10
8.5. Post-Market Adverse Reactions ............................................................................. 12
- 9.
Drug Interactions ........................................................................................................... 12
9.4. Drug-Drug Interactions ........................................................................................... 12
9.7. Drug-Laboratory Test Interactions ......................................................................... 13
- 10.
Clinical Pharmacology ................................................................................................... 13
10.1. Mechanism of Action .............................................................................................. 13
- 11. Storage, Stability, and Disposal ...................................................................................... 13
Part 2: Scientific Information ................................................................................................ 14
- 13. Pharmaceutical Information .......................................................................................... 14
- 14.
Clinical Trials .................................................................................................................. 14
14.1. Clinical Trials by Indication ..................................................................................... 14
- 16. Non-Clinical Toxicology .................................................................................................. 15
Patient Medication Information ........................................................................................... 16
Part 1: Healthcare Professional Information
1. Indications
VARILRIX (varicella virus vaccine, live, attenuated (Oka-strain)) is indicated for:
- the active immunization against varicella of healthy individuals from 12 months of age and up.
- the active immunization against varicella of susceptible high risk patients and their susceptible healthy close contacts.
Refer to the Canadian Immunization Guide for further information on use of VARILRIX below 12 months of age1
1.1. Pediatrics
Pediatrics (9 months and older): Clinical data are available for individuals aged 9 months and older (see 14. Clinical Trials).
1.2. Geriatrics
Geriatrics (65 years of age and older): The safety, immunogenicity and efficacy in individuals 65 years of age and older have not been assessed in clinical trials.
2. Contraindications
VARILRIX (varicella virus vaccine, live, attenuated (Oka-strain)) is contraindicated in:
- individuals having shown signs of hypersensitivity after a previous administration of varicella vaccine dose, including anaphylactic reaction.
- individuals with known hypersensitivity to neomycin or any component of the vaccine. A history of contact dermatitis to neomycin is not a contraindication.
individuals with severe humoral or cellular immunodeficiency (see 7. Warnings and Precautions ) such as:
- individuals with primary or acquired immunodeficiency states with a total lymphocyte count less than 1,200 per mm3;
- individuals presenting other evidence of lack of cellular immune competence (e.g. individuals with active leukemias, lymphomas, blood dyscrasias, clinically manifest HIV infection);
- individuals on current or recent immunosuppressive therapy (includes high doses of corticosteroids but not topical or low-dose parenteral corticosteroids). See 7. Warnings and Precautions.
Varicella-containing vaccines are contraindicated in:
- individuals suffering from acute severe febrile illness.
- individuals with active untreated tuberculosis.
1 Local recommendations are provided in the Canadian Immunization guide: May 2025 for varicella vaccines.
- pregnant women. Pregnancy should be avoided for one month after vaccination.
4. Dosage and Administration
4.2. Recommended Dose and Dosage Adjustment
One immunizing dose contains 0.5 mL of reconstituted vaccine.
Children (12 months to 12 years of age, inclusive) should receive 2 doses (0.5 mL each) of VARILRIX to ensure optimal protection against varicella (see 14. Clinical Trials) with a minimum interval of 6 weeks between doses. If official recommendations prescribe, children in this age group may receive a single 0.5 mL dose of VARILRIX.
Adolescents and adults (13 years of age and older) should receive two 0.5 mL doses with a minimum interval of 6 weeks between doses.
For high risk patients, additional doses of vaccine may be required.
4.3. Reconstitution
The diluent (sterile water for injection) and the reconstituted vaccine should be inspected visually for any foreign particulate matter and/or variation of physical aspect prior to reconstitution or administration. In the event of either being observed, do not use the diluent or the reconstituted vaccine.
VARILRIX is presented as a slightly cream to yellowish or pinkish coloured powder in a monodose glass vial.
Instructions for reconstitution of the vaccine with diluent presented in pre-filled syringe
VARILRIX must be reconstituted by adding the entire contents of the pre-filled syringe of diluent to the vial containing the powder.
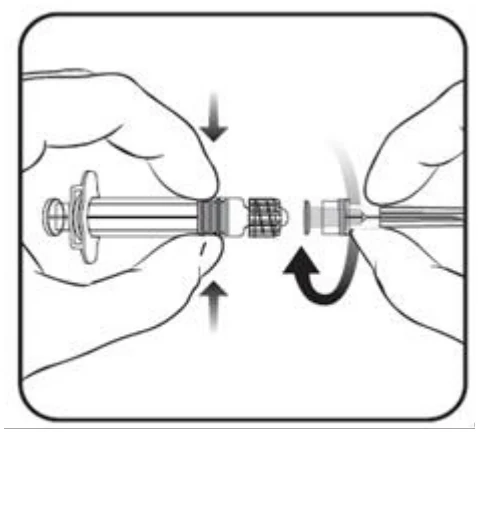
To attach the needle to the syringe, carefully read the instructions given with pictures 1 and 2.
Note: The syringe provided with VARILRIX might be slightly different (without screw thread) than the syringe illustrated. In that case, the needle should be attached without screwing.
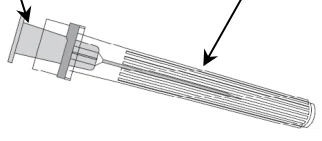
Needle
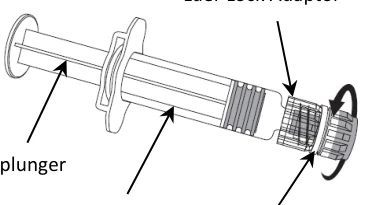
Syringe
Picture 1
Picture 2
Always hold the syringe by the barrel, not by the syringe plunger or the Luer Lock Adaptor (LLA), and maintain the needle in the axis of the syringe (as illustrated in picture 2). Failure to do this may cause the LLA to become distorted and leak.
During assembly of the syringe, if the LLA comes off, a new vaccine dose (new syringe and vial) should be used.
- 1. Unscrew the syringe cap by twisting it anticlockwise (as illustrated in picture 1).
- 2. Attach the needle to the syringe by gently connecting the needle hub into the LLA and rotate a quarter turn clockwise until you feel it lock (as illustrated in picture 2).
- 3. Remove the needle protector, which may be stiff.
- 4. Add the diluent to the vial of powder. The mixture should be well shaken until the powder is completely dissolved in the diluent.
After reconstitution, the vaccine should be used promptly.
- 5. Withdraw the entire contents of the vial of reconstituted vaccine.
- 6. A new needle should be used to administer the vaccine. Unscrew the needle from the syringe and attach the injection needle by repeating step 2 above.
Due to minor variations in pH, the colour of the reconstituted vaccine may vary from clear peach to pink coloured solution. This is normal and does not impair the performance of the vaccine. In the event of other variation being observed, do not use the vaccine.
Alcohol and other disinfecting agents must be allowed to evaporate from the skin before injection of the vaccine since they may inactivate the virus. VARILRIX should not be mixed with other vaccines in the same syringe.
After reconstitution, it is recommended that the vaccine be injected promptly. However, it has been demonstrated that the reconstituted vaccine may be kept for up to 90 minutes at room temperature
Syringe barrel
Syringe plunger
Luer Lock Adaptor
Syringe cap
Needle protector
Needle hub
(25°C) and up to 8 hours in the refrigerator (2 to 8°C). If not used within these timeframes, the reconstituted vaccine must be discarded.
Any unused product or waste material should be disposed of in accordance with local requirements.
4.4. Administration
VARILRIX (varicella virus vaccine, live, attenuated (Oka-strain)) should be administered by subcutaneous injection in the deltoid region.
VARILRIX must not be administered intravascularly or intradermally.
5. Overdose
Cases of accidental administration of more than the recommended dose of VARILRIX have been reported. Amongst these cases, the following adverse events were reported: lethargy and convulsions. In the other cases reported as overdose there were no associated adverse events.
For the most recent information in the management of a suspected drug overdose, contact your regional poison control centre or Health Canada’s toll-free number, 1-844 POISON-X (1-844-764-7669).
- 6. Dosage Forms, Strengths, Composition, and Packaging
Table 1 – Dosage Forms, Strengths, and Composition
Description
VARILRIX (varicella virus vaccine, live, attenuated (Oka-strain)) is a live-attenuated varicella vaccine which contains the Oka-strain of the attenuated varicella-zoster virus. VARILRIX has been reformulated through the addition of a stabilizer, without modification of the viral strain, to permit storage at 2 to 8°C.
VARILRIX is presented as a slightly cream to yellowish or pinkish coloured powder and the diluent, sterile water for injection (WFI), presents as a clear and colourless solution.
Due to minor variations in pH, the colour of the reconstituted vaccine may vary from clear peach to pink coloured solution.
Dosage Form
VARILRIX is supplied as a sterile powder in a vial and the diluent (sterile water for injection, WFI) in a prefilled syringe for subcutaneous injection. The vaccine must be reconstituted and shaken to ensure a uniform mixture before administration.
| Route of Administration | Dosage Form / Strength/Composition | Non-Medicinal Ingredients |
| Subcutaneous injection | Lyophilized powder for injection / Not less than 103.3 plaque-forming units of the varicella-zoster virus per 0.5 mL of reconstituted vaccine | amino acids, lactose, mannitol, sorbitol, and water for injection. Residues: neomycin sulphate. |
Packaging
VARILRIX is supplied in packages of 10 as single monodose vials of lyophilized powder with prefilled syringes of diluent (sterile WFI), with or without needle(s).
Vials/prefilled syringes are made of neutral type I glass.
7. Warnings and Precautions
General
As with other vaccines, the administration of VARILRIX should be postponed in individuals suffering from acute severe febrile illness. In healthy individuals the presence of a minor infection, however, is not a contraindication for vaccination.
As with any parenteral vaccine, appropriate medication (e.g. epinephrine 1:1000) and supervision should be readily available for immediate use in case of anaphylaxis or anaphylactoid reactions following administration of the vaccine.
Syncope (fainting) can occur following, or even before, any vaccination as a psychogenic response to the needle injection. It is important that procedures are in place to avoid injury from faints.
VARILRIX must not be administered intravascularly or intradermally. Accidental intravascular administration may give rise to severe reactions or even shock. Immediate measures depend on the severity of the reaction.
Alcohol and other disinfecting agents must be allowed to evaporate from the skin before injection of the vaccine since they can inactivate the attenuated virus in the vaccine.
VARILRIX can be administered at the same time as any other vaccine. Inactivated vaccines can be administered in any temporal relationship to VARILRIX.
Different injectable vaccines should always be administered at different injection sites.
If a measles vaccine cannot be administered at the same time as VARILRIX, it is recommended that an interval of at least one month be allowed between the administration of the two vaccines as it is recognized that measles vaccination may lead to short lived suppression of the cell mediated immune response.
Limited protection against varicella may be obtained by vaccination up to 72 hours after exposure to natural disease.
As with any vaccine, a protective immune response may not be elicited in all vaccinees.
As for other varicella vaccines, cases of varicella disease have been shown to occur in persons who have previously received VARILRIX. These breakthrough cases are usually mild, with a fewer number of lesions and less fever as compared to cases in unvaccinated individuals.
Transmission of the Oka vaccine virus has been shown to occur at a very low rate in seronegative contacts of vaccine recipients with rash. Transmission of the Oka vaccine from a vaccinee who does not develop a rash to seronegative contacts cannot be excluded. The mild nature of the rash in the healthy contacts indicates that the virus remains attenuated after passage through human hosts.
Encephalitis has been reported during post-marketing use of live attenuated varicella vaccines including PRIORIX-TETRA. In a few cases fatal outcomes have been observed, especially in patients who were immunocompromised (see 2. Contraindications). Vaccinees or parents should be instructed to seek prompt medical attention if they or their child experience, after vaccination, symptoms suggestive of encephalitis such as loss or reduced levels of consciousness, convulsions or ataxia accompanied by fever and headache.
High risk patients: VARILRIX should not be administered at the same time as other live attenuated vaccines. Inactivated vaccines may be administered in any temporal relationship to VARILRIX given that no specific contraindication has been established.
Patients with acute leukemia
Patients suffering from leukemia have been recognized to be at special risk when they develop varicella, and should receive the vaccine if they have no history of the disease or are found to be seronegative.
When vaccinating patients in the acute phase of leukemia, maintenance chemotherapy should be withheld one week before and one week after immunization. Patients under radiotherapy should normally not be vaccinated during the treatment phase.
Generally, patients are immunized when they are in complete hematological remission from the disease. It is advised that the total lymphocyte count should be at least 1,200 per mm3, or that no other evidence of lack of cellular immune competence exists.
Patients under immunosuppressive treatment
Patients under immunosuppressive treatment (including high dose corticosteroid therapy) for malignant solid tumour or for serious chronic diseases (such as chronic renal failure, auto-immune diseases, collagen diseases, severe bronchial asthma) are predisposed to severe varicella.
Vaccination with a live attenuated vaccine, such as varicella, can result in a more extensive vaccine- associated rash or disseminated disease in individuals on immunosuppressant doses of corticosteroids. Individuals who are on immunosuppressant drugs are more susceptible to infections than healthy individuals.
It is advised that the total lymphocyte count should be at least 1,200 per mm3, or that no other evidence of lack of cellular immune competence exists at the time of vaccination.
Patients with planned organ transplantation
If organ transplantation (e.g. kidney transplant) is being considered, vaccination should be carried out 6-8 weeks before the administration of the immunosuppressive treatment.
Patients with chronic diseases
Other chronic disease, such as metabolic and endocrine disorders, chronic pulmonary and cardiovascular diseases, mucoviscidosis and neuromuscular abnormalities may also predispose to severe varicella.
Healthy close contacts
Susceptible healthy close contacts should be vaccinated in order to reduce the risk of the transmission of virus to high risk patients. These include parents and siblings of high risk patients, medical and paramedical personnel, and other people who are in close contact with varicella patients or high risk patients.
Immune
There are limited data on the use of VARILRIX in immunocompromised individuals, therefore vaccination should be considered with caution and only when, in the opinion of the physician, the benefits outweigh the risks.
Immunocompromised individuals who have no contraindication for this vaccination (see 2. Contraindications) may not respond as well as immunocompetent individuals, therefore some of these individuals may acquire varicella despite appropriate vaccine administration. Immunocompromised individuals should be monitored carefully for signs of varicella.
Due to the potential risk of decreased vaccine response and/or disseminated disease, consideration should be given to the time interval between VARILRIX vaccination and immunosuppressive therapy (see 2. Contraindications).
Very few reports exist on disseminated varicella with internal organ involvement following vaccination with Oka varicella vaccine strain mainly in immunocompromised individuals.
7.1. Special Populations
7.1.1. Pregnancy
Pregnant women must not be vaccinated with VARILRIX. Pregnancy should be avoided for one month after vaccination. Women of reproductive age or those who intend to become pregnant should be advised to delay pregnancy.
Adequate human data on the use of VARILRIX during pregnancy are not available and animal studies on reproductive toxicity have not been conducted.
7.1.2. Breastfeeding
It is not known whether VARILRIX is excreted in human milk. Because many drugs are excreted in human milk, caution should be exercised when VARILRIX is administered to breastfeeding women.
7.1.3. Pediatrics
Pediatrics (9 months and older): Clinical data are available for individuals aged 9 months and older (see 14. Clinical Trials). The safety and efficacy of VARILRIX have not been established in children who are known to be infected with human immunodeficiency viruses with and without evidence of immunosuppression (see 2 Contraindications).
8. Adverse Reactions
8.1. Adverse Reaction Overview
VARILRIX (varicella virus vaccine, live, attenuated (Oka-strain)) is a vaccine of low overall reactogenicity in all age groups.
8.2. Clinical Trial Adverse Reactions
Clinical trials are conducted under very specific conditions. Therefore, the frequencies of adverse reactions observed in the clinical trials may not reflect frequencies observed in clinical practice and should not be compared to frequencies reported in clinical trials of another drug.
Healthy subjects
More than 7,900 individuals have participated in clinical trials evaluating the reactogenicity profile of the vaccine administered alone or concomitantly with other vaccines.
The safety profile presented below is based on a total of 5,369 doses of VARILRIX administered in monotherapy to children, adolescents and adults.
Very Common ≥ 10%
General disorders and administration site conditions: pain, redness
Common ≥ 1% and < 10%
Skin and subcutaneous tissue disorders: rash
General disorders and administration site conditions: swelling at the injection sitea, fever (oral/axillary temperature ≥ 37.5°C or rectal temperature ≥ 38.0°C)a
Uncommon ≥ 0.1% and < 1%
Infections and infestations: upper respiratory tract infection, pharyngitis
Blood and lymphatic system disorders: lymphadenopathy
Psychiatric disorders: irritability
Nervous system disorders: headache, somnolence
Respiratory, thoracic and mediastinal disorders: cough, rhinitis
Gastrointestinal disorders: nausea, vomiting
Skin and subcutaneous tissue disorders: varicella-like rash, pruritus
Musculoskeletal and connective tissue disorders: arthralgia, myalgia
General disorders and administration site conditions: fever (oral/axillary temperature > 39.0°C or rectal temperature > 39.5°C), fatigue, malaise
Rare ≥ 0.01% and < 0.1%
Eye Disorders: conjunctivitis
Gastrointestinal disorders: abdominal pain, diarrhea
Skin and subcutaneous tissue disorders: urticaria
a Swelling at the injection site and fever were reported very commonly in studies conducted in adolescents and adults. Swelling was also reported very commonly after the second dose in children under 13 years of age.
A trend for a higher incidence of pain, redness, and swelling after the second dose was observed as compared to the first dose in children under 13 years of age.
The reactogenicity after the second dose in adolescents and adults was not higher than after the first dose. No difference was seen in the reactogenicity profile between initially seropositive and seronegative subjects.
High risk patients
Reactions at the site of injection (redness, swelling and pain) of VARILRIX are usually mild.
Papulo-vesicular eruptions, rarely accompanied by mild to moderate fever, have appeared a few days up to several weeks after immunization. Such reactions have occurred in less than a quarter of leukemic patients. These eruptions were generally mild and short lived.
Eruptions tend to occur in the more immunocompromised leukemic patients such as those still in the maintenance phase of chemotherapy. The appearance of these eruptions did not influence the clinical management of the patients. There is no evidence that immunization may have an adverse effect on the course of the disease.
8.5. Post-Market Adverse Reactions
Following widespread use of the vaccine, the following events have been rarely reported in temporal association with VARILRIX vaccination.
Infections and infestations: herpes zoster
Blood and lymphatic system disorders: thrombocytopenia
Immune system disorders: hypersensitivity, anaphylactic reactions
Nervous system disorders: encephalitis (see 7. Warnings and Precautions, Immune), cerebrovascular accident, cerebellitis, cerebellitis like symptoms (including transient gait disturbance and transient ataxia), convulsions
Encephalitis has been observed following vaccination with live attenuated varicella vaccines. Fatal outcome was reported in a few cases, especially in immunocompromised people.
Vascular disorders: vasculitis (including Henoch Schonlein purpura and Kawasaki syndrome)
Skin and subcutaneous tissue disorders: erythema multiforme
9. Drug Interactions
9.4. Drug-Drug Interactions
In individuals who have received immune globulins or a blood transfusion, vaccination should be delayed for at least three months because of the likelihood of vaccine failure due to passively acquired varicella antibodies.
VARILRIX can be administered at the same time as any other vaccine. Inactivated vaccines can be administered in any temporal relationship to VARILRIX.
Should a measles-containing vaccine not be given at the same time as VARILRIX, it is recommended that an interval of at least one month should be respected since it is recognised that measles vaccination may lead to short-lived suppression of the cell mediated immune response.
Individuals at high risk of severe varicella
VARILRIX should not be administered at the same time as other live attenuated vaccines. Inactivated vaccines may be administered in any temporal relationship to VARILRIX, given that no specific contraindication has been established. However, different injectable vaccines should always be administered at different injection sites.
Salicylates should be avoided for 6 weeks after varicella vaccination, as Reye’s Syndrome has been reported following the use of salicylates during natural varicella infection.
9.7. Drug-Laboratory Test Interactions
If tuberculin testing has to be done it should be carried out before or simultaneously with vaccination since it has been reported that live viral vaccines may cause a temporary depression of tuberculin skin sensitivity. As this anergy may last up to a maximum of 6 weeks, tuberculin testing should not be performed within that period after vaccination to avoid false negative results.
10. Clinical Pharmacology
10.1. Mechanism of Action
VARILRIX is a live, attenuated vaccine made from the Oka strain of varicella-zoster vaccine (VZV). In general, live attenuated viral vaccines contain whole, weakened viruses that have the capacity to replicate within a host. VARILRIX induces a mild, usually inapparent version of VZV infection in susceptible patients that resembles natural infection and in turn trains the immune system through induction of humoral and cell-mediated immune responses. The relative contributions of humoral immunity and cell-mediated immunity to protection from VZV are unknown.
- 11. Storage, Stability, and Disposal
The lyophilized vaccine should be stored in a refrigerator at 2 to 8°C. The diluent (sterile water for injection) may be stored in the refrigerator or at ambient temperature (maximum 25°C). The lyophilized vaccine is not affected by freezing.
The reconstituted vaccine may be kept for up to 90 minutes at room temperature (25°C) and up to 8 hours in the refrigerator (2 to 8°C). If not used within these timeframes, the reconstituted vaccine must be discarded.
Do not use beyond the expiry date printed on the label.
Keep out of the reach and sight of children.
Part 2: Scientific Information
13. Pharmaceutical Information
Drug Substance
Non-proprietary name of the drug substance: varicella virus vaccine, live, attenuated (Oka-strain)
Physicochemical properties: after reconstitution, the pH of the VARILRIX is between 6.9 and 7.4
Product Characteristics:
VARILRIX (varicella virus vaccine, live, attenuated (Oka-strain)) is a live-attenuated varicella vaccine which contains the Oka-strain of the attenuated varicella-zoster virus. VARILRIX has been reformulated through the addition of a stabilizer, without modification of the viral strain, to permit storage at 2 to 8°C.
14. Clinical Trials
14.1. Clinical Trials by Indication
Healthy subjects
In children aged 11-21 months the seroconversion rate, when measured by ELISA (50 mIU/mL) after vaccination, was 89.6% after one vaccine dose and 100% 6 weeks after the second vaccine dose.
In children aged 9 months to 12 years, the overall seroconversion rate when given VARILRIX was > 98% when measured by Immunofluorescence Assay (IFA) at 6 weeks post-vaccination. In children vaccinated at 12-15 months of age, antibodies persisted for at least 7 years after vaccination with one dose.
In children aged 9 months to 6 years the seroconversion rate, when measured by IFA 6 weeks after vaccination, was 100% after a second vaccine dose. A marked increase of antibody titres was observed following administration of a second dose (5 to 26-fold GMT increase).
In subjects aged 13 years and above, the seroconversion rate when given VARILRIX was 100% when measured by IFA 6 weeks after the second vaccine dose. One year after vaccination, all subjects tested were still seropositive.
In an efficacy study in 10 to 30 month old children during a follow-up of an average of 29.3 months, the protective efficacy was 100% against common clinical cases of varicella (≥ 30 vesicles), after one dose of VARILRIX. Against any cases of varicella (mild case with at least 1 vesicle or papule) protective efficacy of VARILRIX was 88%. However, cases were mild (median number of vesicles was 1; no fever was reported).
Exposure and occurrence of varicella breakthrough cases were examined in subjects who returned for one-, two-, and three-year follow-ups post vaccination (studies -039, -040, and -041 respectively). In this study-set, the investigational arm received two doses of PRIORIX-TERA™ 6 weeks apart (the control group received PRIORIX + VARILRIX for the first dose and PRIORIX alone for the second dose). Cumulatively, during the three-year follow-up, the overall exposure to varicella or zoster after the second dose, was reported as 41.3% in the PRIORIX-TETRA™ group versus 38.0% in the control group. Breakthrough cases were reported in 0.44% (95% CI: 0.01%-2.5%) of PRIORIX-TETRA™ recipients, as opposed to 5.06% (95% CI: 1.4%-12.5%) of children in the control group.
Data suggest a higher level of protection and a decrease in breakthrough varicella following two doses of vaccine than following one dose. However, the number of breakthrough cases is limited in the study precluding any firm conclusion.
High risk patients
In high risk patients the overall seroconversion rate when given VARILRIX was 80%, however, in leukemic patients the overall seroconversion rate was about 90%. In one study, the incidence of herpes zoster in immunized leukemic patients was lower than that observed in naturally infected non immunized leukemic patients. In highly immunosuppressed patients clinically evident varicella has occurred after immunization and vaccine-like virus has been isolated from vesicles.
In high risk patients, periodic measurement of varicella antibodies after immunization with VARILRIX may be indicated in order to identify those who may benefit from re-immunization.
16. Non-Clinical Toxicology
Not applicable.