


Product Monograph - Vesanoid
RECENT MAJOR LABEL CHANGES
| 3 SERIOUS WARNINGS AND PRECAUTIONS | 11/2022 |
| 7 WARNINGS AND PRECAUTIONS, Cardiovascular | 11/2022 |
| 7 WARNINGS AND PRECAUTIONS, Psychiatric | 11/2022 |
TABLE OF CONTENTS
Sections or subsections that are not applicable at the time of authorization are not listed.
RECENT MAJOR LABEL CHANGES ............................................................................................. 2
TABLE OF CONTENTS................................................................................................................ 2
PART I: HEALTH PROFESSIONAL INFORMATION ....................................................................... 4
1 INDICATIONS ................................................................................................................ 4
1.1 Pediatrics ............................................................................................................ 4
1.2 Geriatrics ............................................................................................................ 4
2 CONTRAINDICATIONS................................................................................................... 4
3 SERIOUS WARNINGS AND PRECAUTIONS BOX .............................................................. 5
4 DOSAGE AND ADMINISTRATION .................................................................................. 5
4.1 Dosing Considerations ......................................................................................... 5
4.2 Recommended Dose and Dosage Adjustment ...................................................... 5
4.4 Administration .................................................................................................... 6
4.5 Missed Dose ........................................................................................................ 6
5 OVERDOSAGE ............................................................................................................... 6
6 DOSAGE FORMS, STRENGTHS, COMPOSITION AND PACKAGING................................... 7
7 WARNINGS AND PRECAUTIONS.................................................................................... 7
7.1 Special Populations.............................................................................................. 9
7.1.1 Pregnant women ...........................................................................................9
7.1.2 Breast-feeding ............................................................................................. 10
7.1.3 Pediatrics..................................................................................................... 10
7.1.4 Geriatrics ..................................................................................................... 10
8 ADVERSE REACTIONS.................................................................................................. 10
8.1 Adverse Reaction Overview ............................................................................... 10
8.2 Clinical Trial Adverse Reactions .......................................................................... 10
8.3 Less Common Clinical Trial Adverse Reactions .................................................... 11
8.3.1 Less Common Clinical Trial Adverse Reactions – Pediatrics ............................ 13
8.4 Abnormal Laboratory Findings: Hematologic, Clinical Chemistry and Other Quantitative Data........................................................................................................ 13
8.5 Post-Market Adverse Reactions ......................................................................... 13
9 DRUG INTERACTIONS ................................................................................................. 13
9.1 Serious Drug Interactions................................................................................... 13
9.2 Drug-Interactions Overview ............................................................................... 14
9.4 Drug-Drug Interactions ...................................................................................... 14
9.5 Drug-Food Interactions ...................................................................................... 15
9.6 Drug-Herb Interactions ...................................................................................... 15
9.7 Drug-Laboratory Test Interactions...................................................................... 15
10 CLINICAL PHARMACOLOGY......................................................................................... 15
10.1 Mechanism of Action ................................................................................... 15
10.2 Pharmacodynamics ...................................................................................... 15
10.3 Pharmacokinetics......................................................................................... 15
11 STORAGE, STABILITY AND DISPOSAL........................................................................... 17
12 SPECIAL HANDLING INSTRUCTIONS ............................................................................ 17
PART II: SCIENTIFIC INFORMATION ........................................................................................ 17
13 PHARMACEUTICAL INFORMATION ............................................................................. 17
14 CLINICAL TRIALS ......................................................................................................... 18
15 MICROBIOLOGY.......................................................................................................... 18
16 NON-CLINICAL TOXICOLOGY ....................................................................................... 19
PATIENT MEDICATION INFORMATION ................................................................................... 20
PART I: HEALTH PROFESSIONAL INFORMATION
1 INDICATIONS
Vesanoid (tretinoin, also known as all-trans retinoic acid [ATRA]) is indicated for:
- induction of remission in acute promyelocytic leukemia (APL; FAB classification AML-M3).
Previously untreated patients, as well as patients who relapsed after, or were refractory to standard chemotherapy (daunomycin and cytosine arabinoside or equivalent therapies) may be treated with Vesanoid.
1.1 Pediatrics
Pediatrics: There is limited safety and efficacy information on the use of tretinoin in pediatric patients (see 4.2 Recommended Dose and Dosage Adjustment and 7.1.3 Pediatrics).
1.2 Geriatrics
Geriatrics: There is limited safety and efficacy information on the use of tretinoin in elderly patients compared to younger adult patients (see 7.1.4 Geriatrics).
2 CONTRAINDICATIONS
Tretinoin is contraindicated in patients who are hypersensitive to this drug or to any ingredient in the formulation, including any non-medicinal ingredient, or component of the container. For a complete listing, see 6 DOSAGE FORMS, STRENGTHS, COMPOSITION AND PACKAGING.
Tretinoin is highly teratogenic; therefore, it is contraindicated during pregnancy and in nursing mothers. Tretinoin must not be used by women of child-bearing potential unless effective contraception is practiced for at least one month before beginning therapy, during therapy and at least one month following discontinuation of therapy (see 7.1.1 Pregnant women).
The use of tretinoin in combination with vitamin A, tetracyclines and other retinoids is contraindicated (See 9 DRUG INTERACTIONS).
3 SERIOUS WARNINGS AND PRECAUTIONS BOX
Serious Warnings and Precautions
Teratogenic effect: Tretinoin is highly teratogenic. Its use is contraindicated in pregnant women. Tretinoin must not be used by women of child-bearing potential unless effective contraception is practiced for at least one month before beginning therapy, during therapy and at least one month following discontinuation of therapy (see 2 CONTRAINDICATION and 7.1.1 Pregnant women). Should pregnancy occur, in spite of all precautions, during treatment with tretinoin or within one month after its discontinuation, there is a high risk of severe malformation of the fetus, particularly when tretinoin was given during the first trimester of pregnancy (See 7.1.1 Pregnant women). Differentiation Syndrome (formerly known as Retinoic Acid Syndrome): Differentiation syndrome has been reported in many APL patients treated with tretinoin (approximately 26% in some clinical trials) or in association with arsenic trioxide and may be fatal. Differentiation syndrome may occur with severe symptoms such as fever, dyspnea, acute respiratory distress, pulmonary infiltrates, hypotension, pleural and pericardial effusions, peripheral edema, weight gain and may progress into pulmonary, hepatic, renal and multi-organ failure (See 7 WARNINGS AND PRECAUTIONS, General). |
4 DOSAGE AND ADMINISTRATION
4.1 Dosing Considerations
- Due to limited information on patients with hepatic and/or renal insufficiency, the dose should be decreased to 25 mg/m2 as a precautionary measure.
- Rule out pregnancy prior to administration. See 3 SERIOUS WARNINGS AND PRECAUTIONS BOX and 7.1.1 Pregnant Women.
4.2 Recommended Dose and Dosage Adjustment
Recommended Dose
A total daily dose of 45 mg/m2 body surface divided in two equal doses is recommended for oral administration to APL patients, including pediatric and geriatric patients. This is approximately 8 capsules per adult dose.
Treatment should be continued for 30 to 90 days until complete remission has been achieved.
After completion of remission, a course of consolidation chemotherapy including anthracycline and cytosine arabinoside should be initiated immediately; for example, three courses in 5 to 6 weeks intervals.
If there has been a remission with tretinoin alone, it is not necessary to modify the dose of tretinoin if tretinoin is used with chemotherapy.
Dosage Adjustment
- In cases of moderate and severe differentiation syndrome, temporary interruption of tretinoin therapy should be considered (see 7 WARNINGS AND PRECAUTIONS, General). The treatment with tretinoin may need to be withheld during the initial acute symptomatic period but may be resumed when symptoms resolve.
If intracranial hypertension/pseudotumor cerebri occur, a dose reduction of tretinoin is recommended
- (see 7 WARNINGS AND PRECAUTIONS, Neurologic).
- Dose reduction should be particularly considered for children with intractable headache (see 7.1.3 Pediatrics).
The decision to interrupt or continue therapy should be based on an evaluation of the benefit of the treatment versus the severity of the side effects.
Pediatrics: There is limited safety and efficacy information on the use of tretinoin in children. For children the same treatment regimen as for adults is applicable. The optimal pediatric dose of tretinoin has not yet been established. In an attempt to reduce tretinoin related toxicity, the daily dose administered in children can be reduced to 25 mg/m2.
Renal and Hepatic Impairment: The pharmacokinetics of tretinoin in patients with compromised kidney or liver function have not been studied (see 10.3 Pharmacokinetics). The need for dosage adjustment in patients with renal or hepatic impairment is unknown; however, a reduction of dose to 25 mg/m2 is recommended as a precautionary measure.
4.4 Administration
The capsules should be swallowed whole with water. They should not be chewed. It is recommended to take the capsules with a meal or shortly thereafter.
4.5 Missed Dose
If a dose is missed, it should be taken within 6 hours of the initially missed dose. If 6 hours have passed since the initially missed dose, the dose should be omitted, and the regular dosing schedule should be continued.
5 OVERDOSAGE
In cases of overdose with tretinoin, reversible signs of hypervitaminosis A (headache, nausea, vomiting, mucocutaneous symptoms) can appear. There is no specific treatment in the case of an overdose, however, it is important that the patient is treated in a special hematological unit.
| For management of a suspected drug overdose, contact your regional poison control centre. |
6 DOSAGE FORMS, STRENGTHS, COMPOSITION AND PACKAGING
Table 1 – Dosage Forms, Strengths, Composition and Packaging
Vesanoid (tretinoin) capsules are available in bottles of 100 capsules. The capsules are oval and bicolored with an orange-yellow half and a reddish-brown half.
7 WARNINGS AND PRECAUTIONS
General
Differentiation Syndrome (formerly known as Retinoic Acid Syndrome): During clinical trials hyperleukocytosis has been frequently observed, sometimes associated with the “differentiation syndrome” (DS). DS has been reported in many acute promyelocytic leukaemia patients treated with tretinoin (about 26% in some clinical trials) or in association with arsenic trioxide and may be fatal. Early recognition and treatment of DS is therefore of paramount importance. If symptoms of DS become apparent, treatment with a short course of high doses of corticosteroids (i.e., dexamethasone) should be initiated immediately particularly in patients where the syndrome is suspected but hyperleukocytosis is not observed.
During clinical trials hyperleukocytosis has been frequently observed (75%), sometimes associated with the DS.
For those patients experiencing hyperleukocytosis when they receive tretinoin alone, the DS can be prevented by addition of a full-dose anthracycline-based chemotherapy to the tretinoin regimen based on the white blood cell (WBC) count. The current therapeutic treatment recommendations are the following:
- ♦ Immediate treatment of patients with a WBC count of > 5 x 10⁹/L at diagnosis or at any time with a combination of tretinoin and chemotherapy.
- ♦ Addition of full-dose chemotherapy to tretinoin therapy in patients with a WBC of < 5 x 10⁹/L at day 0 of the treatment with tretinoin and if WBC counts become:
♦ ≥ 6 x 10⁹/L at any time from day 1 to day 6 of treatment
and/or ≥ 10 x 109/L at any time from day 7 to day 10 of treatment and/or ≥ 15x 109/L at any time from day 11 to day 28 of treatment
- ♦ Treatment with dexamethasone (10 mg every 12 hours for up to maximum 3 days or until resolution of the symptoms), if the patient presents early clinical signs of the syndrome.
- ♦ In cases of moderate and severe DS, temporary interruption of tretinoin therapy should be considered.
Mortality and morbidity are reduced by following these treatment recommendations in patients with this syndrome.
Supportive care appropriate for patients with acute promyelocytic leukemia, e.g., prophylaxis for bleeding and prompt treatment of infections, should be maintained during therapy with tretinoin.
| Route of Administration | Dosage Form / Strength/Composition | Non-medicinal Ingredients |
| oral | Capsule 10 mg | Gelatin, glycerol, hydrogenated hydrolyzed starch, hydrogenated soybean oil, iron oxide red, iron oxide yellow, mannitol, partially hydrogenated soybean oil, sorbitol, soybean oil, titanium dioxide, yellow beeswax |
An increased body mass index (BMI) has been identified as a predictor factor for DS. Therefore, patients with increased BMI should be closely monitored during therapy especially in terms of respiratory functions, diuresis, and creatinine levels.
Cardiovascular
Thrombosis
There is a risk of thrombosis (both venous and arterial) which may involve any organ system during the first month of treatment (See 8 ADVERSE REACTIONS). Therefore, caution should be exercised when treating patients with the combination of tretinoin and antifibrinolytic agents such as tranexamic acid, aminocaproic acid or aprotinin (See 9.1 Serious Drug Interactions).
Myocarditis
Myocarditis was reported in APL patients treated with tretinoin and was commonly observed in patients experiencing DS. The most common symptoms of myocarditis included chest pain, dyspnea, fatigue, palpitations, and syncope. Additionally, increased troponin and creatinine kinase values, changes in electrocardiogram with ST-segment elevation, decreased left ventricular ejection fraction, increased wall thickness and pericardial effusion were observed. In patients experiencing myocarditis, symptoms most often occurred within the first days of induction treatment, but in some patients, symptoms occurred only after 3 weeks of treatment. In all cases, urgent treatment is required as myocarditis may be fatal. Possible treatment options are similar to the treatment of the DS and include glucocorticoid therapy and temporary interruption of tretinoin therapy.
Driving and Operating Machinery
The ability to drive or operate machinery might be impaired in patients treated with tretinoin, particularly if they are experiencing dizziness or severe headache.
Exercise caution when driving or operating a vehicle or potentially dangerous machinery.
Hematologic
Hyperleukocytosis
Patients experiencing hyperleukocytosis should be treated with full-dose anthracycline-based chemotherapy. Immediate treatment of patients with white blood cell (WBC) count of ≥ 5 x 10⁹/L at diagnosis or during any time of therapy is recommended.
In terms of combination therapy of tretinoin with arsenic trioxide, the use of hydroxyurea should be considered for treatment of leukocytosis to keep WBC<10.000/μL.
Hepatic/Biliary/Pancreatic
The pharmacokinetics of tretinoin in patients with compromised liver function have not been studied. As with other retinoids, the need for dosage adjustments in patients with hepatic impairment is unknown, however, a reduction of dose to 25 mg/m2 is recommended as a precautionary measure.
Monitoring and Laboratory Tests
Because hypercalcaemia may occur during therapy, serum calcium levels should be monitored. The patient’s hematologic profile, coagulation profile, liver function test results, and triglyceride and cholesterol levels should be monitored frequently.
Neurologic
Tretinoin may cause intracranial hypertension/pseudotumor cerebri. The concomitant use of other agents known to cause intracranial hypertension/pseudotumor cerebri such as tetracyclines might increase the risk of this condition (See 9 DRUG INTERACTIONS).
Psychiatric
Depression, depression aggravated, anxiety, and mood alterations have been reported in patients treated with systemic retinoids, including tretinoin. Particular care should be taken in patients with a history of depression. Patients should be monitored for signs of depression and referred for appropriate treatment if necessary. Awareness by family or friends may be useful to detect mental health deterioration.
Renal
The pharmacokinetics of tretinoin in patients with compromised kidney function have not been studied. As with other retinoids, the need for dosage adjustments in patients with renal impairment is unknown, however, a reduction of dose to 25 mg/m2 is recommended as a precautionary measure.
Reproductive Health: Female and Male Potential
Micro-dosed progestogen preparations (“minipill”) may be an inadequate method of contraception during treatment with tretinoin. Information about mandatory contraception during treatment of women of child-bearing potential has to be considered. See Error! Reference source not found. Pregnant women .
- Teratogenic Risk
Tretinoin is highly teratogenic. See 2 CONTRAINDICATIONS, 3 SERIOUS WARNINGS AND PRECAUTIONS BOX and 7.1.1 Pregnant women .
Skin
Cases of Sweet’s syndrome or acute febrile neutrophilic dermatitis have been reported in patients treated with tretinoin, and responded to corticosteroid treatment.
7.1 Special Populations
7.1.1 Pregnant women
Tretinoin is highly teratogenic. Its use is contraindicated in pregnant women and women who might become pregnant during or within one month of the cessation of treatment.
There is an extremely high risk that a deformed infant will result if pregnancy occurs while taking tretinoin, irrespective of the dose or duration of the treatment. Potentially all exposed fetuses can be affected. Therapy with tretinoin should only be started in a female patient if each of the following conditions is met:
- She is informed by her physicians of the hazards concerning pregnancy during and within one month after treatment with tretinoin.
- She is willing to comply with the mandatory contraception measures.
- Every woman of child-bearing potential who is to undergo treatment with tretinoin uses effective contraception for four weeks before, during and for one month after discontinuation of treatment with tretinoin.
- A negative pregnancy test result must be obtained within the two weeks before commencement of treatment. It is advisable to perform additional pregnancy tests at monthly intervals during therapy.
Should pregnancy occur, in spite of these precautions, during treatment with tretinoin or within one month after its discontinuation, there is a high risk of severe malformation of the fetus particularly when tretinoin was given during the first trimester of pregnancy.
All these measures should be considered in relationship to the severity of the disease and the urgency of the treatment.
There is no experience about the extent of exposure in pregnancy during clinical trials.
7.1.2 Breast-feeding
It is unknown if the drug is excreted in human milk. Precaution should be exercised because many drugs can be excreted in human milk. Because of its teratogenic effects, nursing should be discontinued if therapy with tretinoin is initiated. Tretinoin is contraindicated in nursing mothers (see 2 CONTRAINDICATIONS).
7.1.3 Pediatrics
There is limited safety and efficacy information on the use of tretinoin in pediatric patients.
Pseudotumor cerebri (See 8 ADVERSE REACTIONS) has a higher incidence in pediatric patients than in adults. Clinical trial data show a decreased incidence of pseudotumor cerebri with the use of a lower tretinoin dose, without compromising the outcome results. Therefore, a dose reduction to 25 mg/m2 should be considered for children with toxicity symptoms, such as intractable headache (See 4.2 Recommended Dose and Dosage Adjustment).
7.1.4 Geriatrics
There is limited safety and efficacy information on the use of tretinoin in elderly patients compared to younger adult patients. Elderly patients seemed at least as responsive to therapy as did younger patients, but rates of response and survival were lower in this age setting owing to a higher incidence of early deaths and deaths in remission when conventional treatment with tretinoin and chemotherapy was used.
8 ADVERSE REACTIONS
8.1 Adverse Reaction Overview
Differentiation syndrome has been frequently reported in APL patients treated with tretinoin or in association with arsenic trioxide and may be fatal (see 7 WARNINGS AND PRECAUTIONS, General).
The most frequently observed adverse reactions in persons treated with the recommended daily doses of Vesanoid (in ≥ 25% of the patients) were signs and symptoms of the hypervitaminosis A syndrome (including xeroderma, lip and mouth dryness, cheilitis, rash, edema, nausea, vomiting and bone pain). Headache, fever, shivering, fatigue, back pain, chest pain, dyspnea, coughing, abdominal pain, dermal bleeding, and elevation in serum triglycerides, cholesterol and transaminases may also be observed.
8.2 Clinical Trial Adverse Reactions
Clinical trials are conducted under very specific conditions. The adverse reaction rates observed in the clinical trials may therefore not reflect the rates observed in practice and should not be compared to the rates in the clinical trials of another drug. Adverse reaction information from clinical trials may be useful in identifying and approximating rates of adverse drug reactions in real-world use.
The safety profile of Vesanoid has been evaluated retrospectively in a small number of patients.
The following adverse events, considered remotely, possibly or probably related to drug treatment have been reported in more than 25% of all APL patients treated with Vesanoid in the clinical trials:
Table 2 – Adverse Reactions (≥ 25%) in APL Patients Treated with Vesanoid in Clinical Trials
ADR Preferred Term (MedDRA) System Organ Class | Frequency |
| Gastrointestinal disorders | |
| Nausea | 57.1% |
| Vomiting | 54.3% |
| Cheilitis | 30.0% |
| Abdominal pain | 28.6% |
| General disorders and administration site conditions | |
| Pyrexia | 82.9% |
| Chills | 62.9% |
| Fatigue | 57.1% |
| Edema | 28.6% |
| Musculoskeletal and connective tissue disorders | |
| Back pain | 40.0% |
| Bone pain | 40.0% |
| Chest pain | 28.6% |
| Nervous system disorders | |
| Headache | 85.7% |
| Respiratory, thoracic and mediastinal disorders | |
| Dyspnoea | 60.0% |
| Cough | 31.4% |
| Skin and subcutaneous tissue disorders | |
| Xeroderma | 48.6% |
| Lip dry | 45.7% |
| Rash | 40.0% |
| Skin haemorrhage | 31.4% |
8.3 Less Common Clinical Trial Adverse Reactions
The following adverse events, considered remotely, possibly or probably related to drug treatment have been reported in less than 25% of all APL patients treated with Vesanoid in the clinical trials:
Cardiac disorders:
cardiac failure, cyanosis, heart enlarged, arrhythmias
Eye disorders:
blurred vision, visual disturbance, photophobia, conjunctivitis, decreased vision, changes in visual acuity
Ear and labyrinth disorders:
ear fullness, earache, ear buzzing
Gastrointestinal disorders:
abdominal pain, diarrhea, constipation, blisters in the mouth, stomach upset, dysphagia, buccal mucosa ulceration, stomatitis, flatulence, ulcer, pancreatitis, diminished appetite
General disorders and administration site conditions:
generalized pain, abdominal distension, post traumatic pain, chest discomfort, hypothermia
Immune system disorders:
infection, septicemia, moniliasis
Metabolism and nutrition disorders:
weight changes, edema of extremities, acidosis, gout, dehydration, fluid overload, moonface, elevation in serum creatinine
Musculoskeletal and connective tissue disorders:
musculoskeletal pain
Nervous system disorders:
tachycardia, hypertension, hypotension, pallor, red extremities, dizziness, confusion, intracranial hypertension, lightheaded feeling, flank pain, numbness of extremities, abnormal gait, leg weakness, neurologic reaction, inguinal pain, visual field defects, hyporeflexia, paresthesia
Psychiatric disorders:
generalized weakness, anxiety, lethargy, depression, malaise, insomnia, anorexia, agitation, forgetfulness, confusion state
Renal and urinary disorders:
dysuria, kidney failure, urinary tract infection, micturition frequency, renal insufficiency, cystitis
Respiratory, thoracic and mediastinal disorders:
pleural effusion, nasal congestion, pharyngitis, rale, respiratory insufficiency, asthma-like syndrome, pneumonia, respiratory distress, tachypnea, pharynx irritation, pulmonary infiltration, hypoxia, sinusitis, bronchial asthma
Skin and subcutaneous tissue disorders:
pruritus, increased sweating, alopecia, dry scalp, nasal dryness, nail disorder, photosensitivity reaction, xerophthalmia, erythema
Vascular disorders: flushing, thrombosis (both venous and arterial) involving various sites (e.g., cerebrovascular accident, myocardial infarctions, renal infarct)
8.3.1 Less Common Clinical Trial Adverse Reactions – Pediatrics
There is limited safety information on the use of tretinoin in children. There have been some reports of increased toxicity in children treated with tretinoin, particularly increased intracranial hypertension/ pseudotumor cerebri.
8.4 Abnormal Laboratory Findings: Hematologic, Clinical Chemistry and Other Quantitative Data
Clinical Trial Findings
| Clinical Chemistry |
| Blood triglyceride increased, blood creatinine increased, blood cholesterol increased, transaminases increased |
Post Market Findings
| Clinical Chemistry |
| Histamine level increased |
8.5 Post-Market Adverse Reactions
Blood and lymphatic system disorders: Thrombocytosis, marked basophilia with or without symptomatic hyperhistaminemia (mainly in patients with the rare APL variant associated with basophilic differentiation), leukocytosis
Cardiac disorders: Myocarditis, pericarditis
Infections and infestations: Necrotizing fasciitis
Metabolism and Nutrition Disorders: Hypercalcemia
Musculoskeletal and connective tissue disorders: Myositis, bone pain
Skin and subcutaneous tissue disorders: Sweet’s syndrome, erythema nodosum
Vascular disorders: Vasculitis predominantly involving the skin
9 DRUG INTERACTIONS
9.1 Serious Drug Interactions
Serious Drug Interactions
|
|
9.2 Drug-Interactions Overview
As tretinoin is metabolized by the hepatic P450 system, there is the potential for alteration of pharmacokinetic parameters in patients administered concomitant medications that are also inducers or inhibitors of this system. Medications that generally induce hepatic P450 enzymes include rifampicin, glucocorticoids, phenobarbital and pentobarbital. Medications that generally inhibit hepatic P450 enzymes include ketoconazole, cimetidine, erythromycin, verapamil, diltiazem and ciclosporin.
There are no data on a possible pharmacokinetic interaction between tretinoin and daunorubicin and cytosine arabinoside.
9.4 Drug-Drug Interactions
The drugs listed in this table are based on either drug interaction case reports or studies, or potential interactions due to the expected magnitude and seriousness of the interaction (i.e., those identified as contraindicated).
Table 3 – Established or Potential Drug-Drug Interactions
| Common name | Source of Evidence | Effect | Clinical comment |
| Vitamin A or other retinoids | T | Aggravated symptoms of hypervitaminosis A | Combination is contraindicated. Serious side effects due to hypervitaminosis A are expected. |
| Tetracyclines and other agents known to cause intracranial hypertension/pseudo-tumour cerebri | T | Increased risk for the occurrence of intracranial hypertension/pseu-dotumour cerebri | This combination should be avoided to reduce the risk for this serious side effect. |
| Antifibrinolytic agents such as tranexamic acid, aminocaproic acid and aprotinin | C | Fatal thrombotic events during concomitant treatment. | There is a risk for thrombosis during treatment with tretinoin. Concomitant use of antifibrinolytic agents can aggravate these thrombotic events and should be avoided. |
| Imidazole or triazole antimycotics | C | Increased toxicity of tretinoin due to inhibition of its metabolism. | In case treatment with imidazole or triazole antimycotics is urgently needed, clinicians should be aware of signs and symptoms indicative of tretinoin toxicity. |
| Cytochrome P450 inducers such as rifampicin, glucocorticoids, phenobarbital and pentobarbital | T | Decreased tretinoin plasma levels due to increased metabolism. | Clinical relevance is currently not known. However, since the therapeutic efficacy of tretinoin may be reduced due to low plasma concentrations, concomitant use with CYP450 inducers should be avoided. |
| Cytochrome P450 inhibitors such as ketoconazole, cimetidine, erythromycin, verapamil, diltiazem and ciclosporin | CT | Increased tretinoin plasma levels due to decreased metabolism. | In case of imidazole and triazole antimycotics (see above), this interaction has already been identified to cause tretinoin toxicity. In a clinical trial, ketoconazole was successfully used to increase tretinoin plasma levels by countering its self-induced metabolism. Therefore, clinical effects caused by this interaction largely vary and clinicians should be aware of signs and symptoms indicative of tretinoin toxicity. |
Legend: C = Case Study; CT = Clinical Trial; T = Theoretical
9.5 Drug-Food Interactions
The effect of food on the bioavailability of tretinoin has not been characterized. Since the bioavailability of retinoids, as a class, is known to increase in the presence of food, it is recommended that tretinoin be administered with a meal or shortly thereafter.
9.6 Drug-Herb Interactions
Interactions with herbal products have not been established.
9.7 Drug-Laboratory Test Interactions
Interactions with laboratory tests have not been established.
10 CLINICAL PHARMACOLOGY
10.1 Mechanism of Action
Tretinoin is a natural metabolite of retinol and belongs to the class of compounds known as retinoids, which are structurally related to vitamin A and comprise natural and synthetic analogs.
Acute promyelocytic leukemia (APL) is associated with a non-random chromosomal abnormality characterized by balanced and reciprocal translocations between the long arms of chromosomes 15 and 17 [t(15;17)(q22;q21)]. The gene encoding the retinoic acid receptor-alpha (RAR-α) is located on chromosome 17. A previously unidentified gene, PML, that may act as a transcription factor, is located on chromosome 15. The 15;17 translocation fuses the genes for PML and RAR-α, resulting in the synthesis of two reciprocal fusion transcripts, PML/RAR-α (found in all patients) and RAR-α/PML (found in about 2/3 of patients). PML/RAR-α may inhibit the differentiation of myeloid cells, resulting in carcinogenesis, an effect which may be overcome by the use of high doses of tretinoin.
10.2 Pharmacodynamics
In vitro studies with tretinoin have demonstrated induction of differentiation and inhibition of cell proliferation in transformed hemopoietic cell lines, including human myeloid leukemia cell lines.
10.3 Pharmacokinetics
Table 4 – Summary of Tretinoin Pharmacokinetic Parameters in the Adult Patient Population
| Cmax | Tmax | t½ (h) | Active metabolites | |
|---|---|---|---|---|
| Single dose mean | 0.03 - 2.5 μg/ml | ~ 90 min | 0.71 h | 4-hydroxy-tretinoin, 4-oxo-tretinoin (less effective than tretinoin) |
Absorption:
Tretinoin is an endogenous metabolite of vitamin A and is normally present in plasma at concentrations of 2 to 4 ng/mL. After oral administration, tretinoin is absorbed by the digestive tract. It is transported directly via the portal system rather than through the lymphatics and thus absorption does not require specific transport mechanisms. Maximum plasma concentrations of tretinoin were reached within one to two hours in APL patients. Maximum plasma concentrations in healthy volunteers are attained after 3 hours. There is a large inter-patient and intra-patient variation in plasma levels of tretinoin.
Distribution:
Tretinoin is highly lipophilic with more than 95% of total drug concentration bound to plasma proteins. Following peak levels, plasma concentrations decline with a mean elimination half-life of 0.7 hours. Plasma concentrations return to endogenous levels following a single 40 mg dose after 7 to 12 hours. No accumulation is seen after multiple doses.
Metabolism:
Tretinoin is primarily metabolized by liver enzymes and is converted to the 13-cis isomer. During continuous administration, a marked decrease in plasma concentration can occur, possibly due to cytochrome P450 enzyme induction which increases clearance and decreases bioavailability after oral doses. Among patients maintained on tretinoin, a loss of responsiveness to tretinoin has been reported, with a median time to relapse of 4-6 months. Oxidation by P450 isoenzymes leads to the corresponding 4-hydroxy and 4-oxo-compounds.
Elimination:
Following an oral single dose administration, plasma concentrations of tretinoin declined mono-exponentially with a mean elimination half-life of 0.71 hours. Endogenous levels (2 to 4 ng/mL) were reached 7 to 12 hours after dosing.
After glucuronidation, the 4-hydroxy and 4-oxo-compounds are excreted in the urine and bile. Following a single dose of radiolabelled tretinoin, about 30% of the total radioactivity was recovered in the feces and about 60% in the urine. Nearly the entire dose was excreted within 3 to 6 days.
Special Populations and Conditions:
Multiple Doses: Multiple oral doses of tretinoin were associated with a significant (about 2-fold) decrease in both the peak plasma levels and the AUC levels, after 2-6 weeks of treatment. These changes were associated with a 10-fold increase in urinary excretion of 4-oxo all-trans retinoic acid glucuronide.
The administration of ketoconazole, an inhibitor of the P450 enzyme system, after multiple doses of tretinoin resulted in a greater mean plasma tretinoin AUC than after the administration of tretinoin alone.
Pediatrics: A phase I trial of tretinoin administered orally twice a day for treatment courses of 28 days was performed in pediatrics. Cohorts of at least 3 patients were entered at successive tretinoin dose levels (from 45 to 80 mg/m2/day, with a twice a day dosing regimen) until dose-limiting toxicity was consistently observed. Twenty-one patients with a median age of 14 years and various types of tumours including 2 patients with APL were entered into the trial.
Pharmacokinetics were determined in eighteen patients on day one and in seven patients on day 1 and day 28. Time to peak plasma concentrations was between 1 and 4 hours after dosing. Peak plasma concentrations of tretinoin of 0.59, 0.62 and 1.64 μM (180, 190 and 490 ng/mL) were observed following doses of 22.5, 30 and 40 mg/m2. AUC values for these doses were 1.29, 1.13 and 3.35 μM (387, 339 and 1005 ng.h/mL), respectively. Peak plasma concentrations and AUC values did not appear to increase in proportion to dose. A greater than three-fold increase in AUC was observed following a 30% increase in dose (30 to 40 mg/m2). The average terminal half-life was 0.7 hours. The AUC on day 1 was significantly greater than the AUC on day 28 (mean decrease 78% ± 30 SD). Quantifiable concentrations of 4-oxo metabolites of tretinoin were not observed.
Hepatic Insufficiency: The pharmacokinetics of tretinoin in patients with compromised liver function have not been studied. As a precautionary measure, the dose will be decreased to 25 mg/m2/day (See 4.1 Dosing Considerations).
Renal Insufficiency: The pharmacokinetics of tretinoin in patients with compromised kidney function have not been studied. As a precautionary measure, the dose will be decreased to 25 mg/m2/day (See 4.1 Dosing Considerations).
11 STORAGE, STABILITY AND DISPOSAL
Keep the bottle tightly closed; store at 15-30°C. Protect from light.
12 SPECIAL HANDLING INSTRUCTIONS
Broken capsules should be disposed of without touching or wearing rubber gloves to avoid exposure to the drug.
PART II: SCIENTIFIC INFORMATION
13 PHARMACEUTICAL INFORMATION
Drug Substance
Proper name: Tretinoin (also known as all-trans retinoic acid)
Chemical name: 3,7-dimethyl-9-(2,6,6-trimethylcyclohex-1-enyl)nona-2,4,6,8-all-trans tetraenoic acid
Molecular formula and molecular mass: C20H28O2 300.44 g/mol
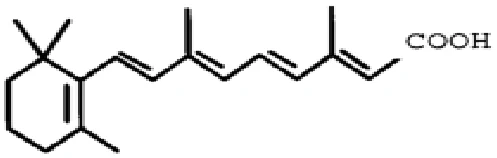
Structural formula:
Physicochemical properties: Yellow to light-orange crystalline powder with very low solubility in water. Slightly soluble in alcohol and in chloroform. It is very sensitive to light and oxygen.
14 CLINICAL TRIALS
The clinical trial data on which the original indication was authorized is not available.
15 MICROBIOLOGY
No microbiological information is required for this drug product.
16 NON-CLINICAL TOXICOLOGY
General Toxicology: Symptoms of acute toxicity in LD50 studies in mice and rats included sedation, hair loss, respiratory depression, blood encrusted eyes, swollen eyelids, changes in skin texture, cachexia, diuresis, diarrhea and salivation. The 10 days LD50 values were between 2,200 to 2,600 mg/kg and 2,000 mg/kg for mice and rats, respectively.
In subchronic (up to 13 weeks) and chronic (up to 440 days) toxicity studies in rats, symptoms were dose-related (up to 50 mg/kg/day) and included increased serum alkaline phosphatase, reduced body weight, testicular degeneration, bone fractures, increased liver weight and decrease in red blood cells.
Carcinogenicity: In carcinogenicity studies in mice, tretinoin had different effects on the incidence of chemically induced tumors. Tretinoin was either tumor-enhancing, tumor-inhibiting or had no effect at all. Tretinoin alone was shown to have no carcinogenic effects.
Genotoxicity: Tretinoin did not show genotoxic effects in the preclinical studies.
Reproductive and Developmental Toxicology: Tretinoin showed embryotoxic and teratogenic effects in several studies involving different species such as rats, mice, hamsters, rabbits and monkeys. Effects were shown to be dose-dependent and included malformations and fetal resorption.
In one study conducted in rats with doses up to 5 mg/kg p.o., no effects on the fertility or reproductive capacity of male and female adult rats were shown. However, survival of their offspring was reduced.