


Product Monograph - Viskazide
Recent Major Label Changes
| 2026-09 |
|---|---|
| 2026-09 |
| 2026-09 |
| 2026-09 |
| 2026-09 |
Table of Contents
Recent Major Label Changes ................................................................................................... 2
Table of Contents ................................................................................................................... 2
- 1.
Indications ....................................................................................................................... 4
1.1. Pediatrics .................................................................................................................. 4
1.2. Geriatrics .................................................................................................................. 4
- 2. Contraindications ............................................................................................................ 4
- 4.
Dosage and Administration ............................................................................................. 5
4.1. Dosing Considerations .............................................................................................. 5
4.2. Recommended Dose and Dosage Adjustment ......................................................... 5
4.4. Administration .......................................................................................................... 5
4.5. Missed Dose ............................................................................................................. 5
- 5. Overdose ......................................................................................................................... 6
- 6. Dosage Forms, Strengths, Composition, and Packaging ................................................... 7
- 7.
Warnings and Precautions ............................................................................................... 7
General ................................................................................................................................. 7
Carcinogenesis and Genotoxicity .......................................................................................... 7
Cardiovascular ...................................................................................................................... 8
Endocrine and Metabolism ................................................................................................... 9
Hepatic/Biliary/Pancreatic .................................................................................................. 10
Immune .............................................................................................................................. 10
Ophthalmologic .................................................................................................................. 11
Renal ................................................................................................................................... 11
Reproductive Health ........................................................................................................... 11
Respiratory ......................................................................................................................... 12
Sensitivity/Resistance ......................................................................................................... 12
Skin ..................................................................................................................................... 12
7.1. Special Populations ................................................................................................ 12
7.1.1. Pregnancy ...................................................................................................... 12
7.1.2. Breastfeeding ................................................................................................ 13
7.1.3. Pediatrics (< 18 years of age) ......................................................................... 13
7.1.4. Geriatrics (> 65 years of age) ......................................................................... 13
- 8.
Adverse Reactions ......................................................................................................... 13
8.1. Adverse Reaction Overview .................................................................................... 13
8.4. Abnormal Laboratory Findings: Hematologic, Clinical Chemistry, and Other Quantitative Data ............................................................................................................... 14
8.5. Post-Market Adverse Reactions ............................................................................. 14
- 9.
Drug Interactions ........................................................................................................... 15
9.4. Drug-Drug Interactions ........................................................................................... 15
9.5. Drug-Food Interactions........................................................................................... 21
9.6. Drug-Herb Interactions ........................................................................................... 21
9.7. Drug-Laboratory Test Interactions ......................................................................... 21
- 10.
Clinical Pharmacology ................................................................................................... 22
10.1. Mechanism of Action .............................................................................................. 22
10.2. Pharmacodynamics ................................................................................................ 22
10.3. Pharmacokinetics ................................................................................................... 24
- 11. Storage, Stability, and Disposal ...................................................................................... 25
Part 2: Scientific Information ................................................................................................ 26
- 13. Pharmaceutical Information .......................................................................................... 26
- 16. Non-Clinical Toxicology .................................................................................................. 27
Patient Medication Information ........................................................................................... 33
Part 1: Healthcare Professional Information
1. Indications
VISKAZIDE (pindolol and hydrochlorothiazide) is indicated for:
- The maintenance therapy of patients with hypertension who require pindolol and hydrochlorothiazide in the dosage and ratios present in VISKAZIDE.
This fixed combination is not indicated for initial therapy of hypertension. Hypertension requires therapy titrated to the individual patient. It is always better to adjust the dosage of each antihypertensive drug separately, but when the fixed combination corresponds to the optimum drug and dose requirements of the patient, its use may be more convenient in patient management. For further adjustment of dosage, however, it is best to use the individual drugs again. The treatment of hypertension is not static, but must be re-evaluated as conditions in each patient warrant.
1.1. Pediatrics
Pediatrics (< 18 years of age): No data are available to Health Canada; therefore, Health Canada has not authorized an indication for pediatric use.
1.2. Geriatrics
Geriatrics (> 65 years of age): No evidence exists that geriatric patients require different dosages of pindolol; however, these patients should be treated cautiously. (See 7. Warnings and Precautions; 7.1.4 Geriatrics and 10. Clinical Pharmacology; Special populations and conditions)
2. Contraindications
VISKAZIDE is contraindicated in:
- Congestive heart failure (see 7. Warnings and Precaution)
- Right ventricular failure secondary to pulmonary hypertension
- Significant cardiomegaly
- Sinus bradycardia (< 45 -50 beats/min)
- Second and third degree A-V block
- Cardiogenic shock
- Bronchospasm (including bronchial asthma), or severe chronic obstructive pulmonary disease (see 7. Warnings and Precaution)
- Anesthesia with agents that produce myocardial depression, e.g., ether
- Anuria
- Hypersensitivity to pindolol, hydrochlorothiazide, or to sulfonamide-derived drugs, or cross-sensitivity to other beta blockers
- Prinzmetal's angina (variant angina)
- Sick sinus syndrome
- Severe peripheral arterial circulatory disturbances
- Untreated pheochromocytoma
4. Dosage and Administration
4.1. Dosing Considerations
- Dosage must be determined for individual patients by titration of each component separately. Where the fixed combination in VISKAZIDE (pindolol and hydrochlorothiazide) supplies the dosage so determined, the combination product may be used for maintenance therapy.
- If higher doses of either ingredient are needed, the individual components should be used.
- When necessary, another antihypertensive agent may be added gradually, beginning with 50% of the usual recommended starting dose to avoid excessive reduction in blood pressure.
- If dosage adjustment is necessary during maintenance therapy, it is advisable to use the individual drugs.
4.2. Recommended Dose and Dosage Adjustment
One or two VISKAZIDE tablets once daily in the morning can be used to administer up to 20 mg pindolol and 100 mg hydrochlorothiazide
- Patients with impaired renal function/ hepatic function: Patients with impaired renal or hepatic function may usually be treated with normal doses of pindolol. Only in severe cases may a reduction of the daily dose be necessary (See 10. Clinical Pharmacology; Special Populations).
- Pediatrics (< 18 years of age): Health Canada has not authorized an indication for pediatric use.
- Geriatrics (> 65 years of age): No evidence exists that geriatric patients require different dosages of pindolol; however, these patients should be treated cautiously. (See 7. Warnings and Precautions and 10. Clinical Pharmacology; Special Populations)
If a diagnosis of acute respiratory distress syndrome (ARDS) is suspected, VISKAZIDE should be withdrawn and the appropriate treatment given.
4.4. Administration
VISKAZIDE should be taken as a single dose in the morning. If VISKAZIDE causes stomach upset, it may be taken with food or milk.
4.5. Missed Dose
If a dose is missed during the day, the missed dose should be skipped and the next dose should be taken at the usual scheduled time. Do not take a double dose to make up for a missed dose.
5. Overdose
An overdosage of beta-blocker such as pindolol may lead to pronounced bradycardia, hypotension, cardiac failure, cardiogenic shock, conduction abnormalities, cardiac arrest, dyspnea, bronchospasm, vomiting, hypoglycemia, depressed levels of consciousness, generalized convulsions, coma and death. In rare circumstances, overdose of beta-blockers with intrinsic sympathomimetic activity (ISA), like pindolol, may present with tachycardia and hypertension. Concomitant ingestion of alcohol, antihypertensives, antidepressants, or antiarrhythmic may aggravate the signs and symptoms of overdose.
The hydrochlorothiazide component may cause excessive diuresis with electrolyte depletion and dehydration. Signs are dry mouth, thirst, weakness, lethargy, drowsiness, restlessness, muscle pains or cramps, muscular fatigue, hypotension, oliguria, tachycardia, gastrointestinal disturbances, mental confusion, delirium, convulsions, shock and coma.
If digitalis has also been administered, hypokalemia may accentuate myocardial abnormalities (e.g. cardiac arrhythmias).
Hydrochlorothiazide may precipitate hepatic coma in cirrhotics, potentiate other antihypertensive agents and decrease responsiveness to norepinephrine.
Treatment:
Discontinue VISKAZIDE. There is no specific antidote. If ingestion is, or may have been, recent, gastric lavage or emesis may reduce absorption; when ingestion has been earlier, infusions may be helpful to promote urinary excretion.
If required, the following therapeutic measures are suggested:
- 1. Bradycardia: Atropine or another anticholinergic drug.
- 2. Heart block: (second or third degree) Isoproterenol or transvenous cardiac pacemaker.
- 3. Congestive heart failure: Conventional therapy.
- 4. Hypotension: (depending on associated factors) Epinephrine rather than isoproterenol or norepinephrine may be useful in addition to atropine and digitalis.
- 5. Bronchospasm: Aminophylline or isoproterenol.
- 6. Hypoglycemia: Intravenous glucose.
- 7. Stupor or Coma: Administer supportive therapy as clinically warranted.
- 8. Gastrointestinal Effects: Though usually of short duration, these may require symptomatic treatment.
- 9. Abnormalities in BUN and/or Serum Electrolytes: Monitor serum electrolyte levels and renal function; institute supportive measures as required individually to maintain hydration, electrolyte balance, respiration and cardiovascular-renal function.
It should be remembered that pindolol is a competitive antagonist of isoproterenol and hence large doses of isoproterenol can be expected to reverse many of the effects of excessive doses of VISKAZIDE.
However, the complications of excess isoproterenol should not be overlooked.
| For the most recent information in the management of a suspected drug overdose, contact your regional poison control centre or Health Canada’s toll-free number, 1-844 POISON-X (1-844-764-7669). |
|---|
- 6. Dosage Forms, Strengths, Composition, and Packaging
Table 1 – Dosage Forms, Strengths, and Composition
Description
VISKAZIDE 10/25: Each peach, round, compressed tablet, 9 mm diameter, one side slope-faced and bisected with "10/25" embossed on each side of the bisect, reverse side flat-faced with bevelled edge and embossed with "VISKAZIDE*" around the circumference, contains: pindolol 10 mg and hydrochlorothiazide 25 mg. Also contains cornstarch. Calendar packs of 35.
VISKAZIDE 10/50: Each orange, round, compressed tablet, 9 mm diameter, one side slope-faced and bisected with "10/50" embossed on each side of the bisect, reverse side flat-faced with bevelled edge and embossed with "VISKAZIDE*" around the circumference, contains: pindolol 10 mg and hydrochlorothiazide 50 mg. Also contains cornstarch. Calendar packs of 35.
7. Warnings and Precautions
General
The antihypertensive effects of thiazides may be enhanced in the postsympathectomy patient.
Carcinogenesis and Genotoxicity
Non-melanoma skin cancer:
An increased risk of non-melanoma skin cancer (NMSC) [basal cell carcinoma (BCC) and squamous cell carcinoma (SCC) of the skin] after hydrochlorothiazide therapy was reported in some epidemiological studies. The risk may be higher with increasing cumulative use (see 8. Adverse Reactions; 8.5 Post-Market Adverse Reactions). The photosensitizing action of hydrochlorothiazide may be a possible mechanism for NMSC (See 16. Non-Clinical Toxicology; Carcinogenicity – Hydrochlorothiazide).
Patients taking hydrochlorothiazide should be informed of the potential risk of NMSC. They should be advised to regularly check their skin for new lesions as well as changes to existing ones, and to promptly report any suspicious skin lesions. Patients should also be advised to limit exposure to sunlight, to avoid the use of indoor tanning equipment, and to use adequate protection (e.g. a broad-spectrum sunscreen with a SPF of 30 or higher, clothing, and a hat) when exposed to sunlight or UV
| Route of Administration | Dosage Form/ Strength/Composition | Non-Medicinal Ingredients |
| Oral | Tablet 10/25mg Tablet 10/50mg | Cellulose microcrystalline, magnesium stearate, pregelatinized starch, silica colloidal anhydrous |
light to minimize the risk of skin cancer.
Alternatives to hydrochlorothiazide may be considered for patients who are at a particularly high risk for NMSC (e.g., light coloured skin, known personal or family history of skin cancer, ongoing immunosuppressive therapy, etc.) (See 8. Adverse Reactions; 8.5. Post-Market Adverse Reaction).
Cardiovascular
Cardiac Failure:
Special caution should be exercised when administering VISKAZIDE (pindolol and hydrochlorothiazide) to patients with a history of heart failure. Sympathetic stimulation is a vital component supporting circulatory function in congestive heart failure, and inhibition with beta-blockade always carries the potential hazard of further depressing myocardial contractility and precipitating cardiac failure.
In patients without a history of cardiac failure, continued depression of the myocardium over a period of time can, in some cases, lead to cardiac failure. Therefore, at the first sign or symptom of impending cardiac failure occurring during therapy with VISKAZIDE, patients should be fully digitalized and/or given additional diuretic therapy, and the response observed closely.
Pindolol acts selectively without blocking the inotropic action of digitalis on heart muscle. However, the positive inotropic action of digitalis may be reduced by the negative inotropic effect of pindolol when the two drugs are used concomitantly. The effects of pindolol and digitalis are additive in depressing AV conduction. If cardiac failure persists, therapy with VISKAZIDE should be discontinued (see below).
Abrupt Cessation of Therapy with VISKAZIDE in Angina Pectoris:
Patients with angina should be warned against abrupt discontinuation of VISKAZIDE. There have been reports of severe exacerbation of angina, and of myocardial infarction or ventricular arrhythmias occurring in patients with angina pectoris, following abrupt discontinuation of beta blocker therapy. The last two complications may occur with or without preceding exacerbation of angina pectoris. Therefore, when discontinuation of VISKAZIDE is planned in patients with angina pectoris, the dosage should be reduced over a period of about two weeks and the patient should continue to be observed. The same frequency of administration should be maintained.
In situations of greater urgency, VISKAZIDE should be discontinued stepwise and under conditions of closer observation. If angina markedly worsens or acute coronary insufficiency develops, it is recommended that treatment with VISKAZIDE be reinstituted promptly, at least temporarily.
Since ischemic heart disease may be unrecognized, the above advice should be followed in patients considered to be at risk of having asymptomatic ischemic heart disease.
Co-medication with calcium channel blockers: Owing to the danger of cardiac arrest, a calcium channel blocker of the verapamil type must not be administered intravenously to a patient already receiving treatment with a beta-blocker.
Sinus bradycardia may occur with the use of pindolol due to unopposed vagal activity remaining after blockade of beta-adrenergic receptors. However, due to its intrinsic sympathomimetic activity (ISA), pindolol causes less bradycardia at rest than some other beta-adrenergic blocking agents. If excessive bradycardia occurs the dosage of VISKAZIDE should be reduced.
Phaeochromocytoma: If patients with phaeochromocytoma are treated with a beta-blocker, an alpha-blocker should always be co-administered. (See 2. Contraindications)
Elective or Emergency Surgery
Beta-adrenergic receptor blockade impairs the ability of the heart to respond to beta-adrenergically mediated reflex stimuli. Some patients receiving beta-adrenergic receptor blocking agents have been subject to protracted severe hypotension during anesthesia. Difficulty in restarting and maintaining the heartbeat has also been reported.
For these reasons, in patients with angina pectoris undergoing elective surgery, some authorities recommend gradual withdrawal of beta-adrenergic receptor blocking agents. (See 7. Warnings and Precautions; Abrupt Cessation of Therapy).
In emergency surgery, since pindolol is a competitive inhibitor of beta-adrenergic receptor agonists its effects may be reversed, if necessary, by sufficient doses of such agonists as isoproterenol or levarterenol.
Epinephrine and Beta-blockers
There may be increased difficulty in treating an allergic type reaction in patients on beta-blockers. In these patients, the reaction may be more severe due to pharmacologic effects of the beta-blockers and problems with fluid changes. Epinephrine should be administered with caution since it may not have its usual effects in the treatment of anaphylaxis. On the one hand, larger doses of epinephrine may be needed to overcome the bronchospasm, while on the other hand, these doses can be associated with excessive alpha-adrenergic stimulation with consequent hypertension, reflex bradycardia and heart block and possible potentiation of bronchospasm. Alternatives to the use of large doses of epinephrine include vigorous supportive care such as fluids and the use of beta agonists including parenteral salbutamol or isoproterenol to overcome bronchospasm and norepinephrine to overcome hypotension.
Patients receiving catecholamine-depleting drugs, such as reserpine or guanethidine, should be closely monitored because the added beta-adrenergic-blocking action of VISKAZIDE may produce an excessive reduction of sympathetic activity. VISKAZIDE should not be combined with other beta-blockers.
The combination of VISKAZIDE with an antihypertensive peripheral vasodilator produces a greater fall in blood pressure than either drug alone. The same degree of blood pressure control can be achieved by lower than usual dosages of each drug. Therefore, when using such combined therapy, careful monitoring of the dosages is required until the patient is stabilized.
Thiazides may decrease arterial responsiveness to norepinephrine. This diminution is not sufficient to preclude the therapeutic effectiveness of the pressor agent in therapy.
Thiazides may increase the responsiveness to tubocurarine.
Orthostatic hypotension may occur and may be potentiated by alcohol, barbiturates or narcotics.
Endocrine and Metabolism
In patients with thyrotoxicosis, pindolol may give a false impression of improvement by diminishing peripheral manifestations of hyperthyroidism without improving thyroid function. Special considerations should be given to the potential of pindolol to aggravate congestive heart failure. Therefore, these patients should be carefully monitored for thyroid function. Patients suspected of developing thyrotoxicosis should be managed carefully to avoid abrupt withdrawal of beta blockade which might precipitate a thyroid storm. Thiazides may decrease serum PBI levels without signs of thyroid disturbance.
Beta-adrenergic receptor blocking agents may mask the premonitory signs and symptoms (e.g. palpitations, tachycardia, tremor) of acute hypoglycaemia whereas sweating is not inhibited. Therefore, VISKAZIDE should be administered with caution to patients subject to spontaneous hypoglycemia, or to diabetic patients (especially those with labile diabetes) who are receiving insulin or oral hypoglycemic agents. Insulin requirements in diabetic patients may be increased, decreased, or unchanged by thiazides. Diabetes mellitus which has been latent may become manifest during administration of thiazide diuretics. The concurrent use of beta-blockers and antidiabetic medication should always be monitored to confirm that diabetic control is well maintained.
Patients receiving thiazides should be carefully observed for clinical signs of fluid and electrolyte imbalance (hyponatremia, hypochloremic alkalosis and hypokalemia). Periodic determination of serum electrolytes should be performed at appropriate intervals. Serum and urine electrolyte determinations are particularly important when the patient is vomiting excessively or receiving parenteral fluids. Warning signs or symptoms of fluid and electrolyte imbalance include dryness of the mouth, thirst, weakness, lethargy, drowsiness, restlessness, muscle pains or cramps, muscular fatigue, hypotension, oliguria, tachycardia, and gastrointestinal disturbances such as nausea and vomiting.
Hypokalemia may develop, especially with brisk diuresis, when severe cirrhosis is present, or during concomitant use of corticosteroids or ACTH. Interference with adequate oral electrolyte intake will also contribute to hypokalemia. Hypokalemia can sensitize or exaggerate the response of the heart to the toxic effects of digitalis (e.g. increased ventricular irritability). Hypokalemia may be avoided or treated by use of potassium supplements, potassium sparing agents or foods with a high potassium content.
Any chloride deficit during thiazide therapy is generally mild and usually does not require specific treatment except under extraordinary circumstances (as in liver disease or renal disease). Dilutional hyponatremia may occur in edematous patients in hot weather; appropriate therapy is water restriction rather than administration of salt, except in rare instances, when the hyponatremia is life threatening. In actual salt depletion, appropriate replacement is the therapy of choice.
Because calcium excretion is decreased by thiazides, VISKAZIDE should be discontinued before carrying out tests for parathyroid function. Pathologic changes in the parathyroid glands, with hypercalcemia and hypophosphatemia, have been observed in a few patients on prolonged thiazide therapy; however, the common complications of hyperparathyroidism such as renal lithiasis, bone resorption, and peptic ulceration have not been seen.
Hyperuricemia may occur or acute gout may be precipitated in certain patients receiving thiazide therapy.
Hepatic/Biliary/Pancreatic
In patients with impaired hepatic function or progressive liver disease, even minor alterations in fluid and electrolyte balance may precipitate hepatic coma. Hepatic encephalopathy, manifested by tremors, confusion, and coma, has been reported in association with diuretic therapy including hydrochlorothiazide.
Immune
Anaphylactic reaction:
Anaphylactic reactions precipitated by other agents may be particularly severe in patients taking beta-blockers, especially non-selective beta-blockers, and may be resistant to normal doses of adrenaline. Whenever possible, beta-blockers should be avoided in patients who are at increased risk for anaphylaxis.
In patients receiving thiazides, sensitivity reactions may occur with or without a history of allergy or bronchial asthma.
The possible exacerbation of activation of systemic lupus erythematosus has been reported with thiazides.
Ophthalmologic
Choroidal Effusion, Acute Myopia and Secondary Angle-Closure Glaucoma related to Hydrochlorothiazide:
Hydrochlorothiazide, a sulfonamide, can cause an idiosyncratic reaction, resulting in choroidal effusion, acute transient myopia and/or acute angle-closure glaucoma. Symptoms include acute onset of decreased visual acuity, blurred vision or ocular pain and typically occur within hours to weeks of drug initiation. Untreated acute angle-closure glaucoma can lead to permanent vision loss.
The primary treatment is to discontinue hydrochlorothiazide as rapidly as possible. Prompt medical or surgical treatments may need to be considered if the intraocular pressure remains uncontrolled. Risk factors for developing acute angle-closure glaucoma may include a history of sulphonamide or penicillin allergy.
Renal
Impaired Renal or Hepatic Function:
ß-blocking agents should be used with caution in patients with impaired hepatic or renal function. Poor renal function has only minor effects on pindolol clearance, but poor hepatic function may cause blood levels of pindolol to increase substantially.
In patients with renal disease, thiazides may precipitate azotemia, and cumulative effects may develop in the presence of impaired renal function. If progressive renal impairment becomes evident, VISKAZIDE should be discontinued.
In patients with severe renal impairment, further impairment of renal function has been only rarely observed during therapy with pindolol.
Lithium generally should not be given with diuretics because they reduce its renal clearance and add a high risk of lithium toxicity. Read Prescribing Information for lithium preparations before use of such preparations with VISKAZIDE.
Reproductive Health
- Fertility
In rats, pindolol did not cause any adverse effects on fertility or reproductive performance at a dose of 10 mg/kg, which is 17-times the human dose. While effects in animals are not always predictive of human effects, at dose levels of 30 mg/kg and greater, female rats were observed to mate less frequently than untreated animals (See 10. Non-Clinical Toxicology).
Respiratory
VISKAZIDE (pindolol and hydrochlorothiazide) should be administered with caution to patients prone to nonallergic bronchospasm (e.g., chronic bronchitis, emphysema) since beta-blockade may block bronchodilatation produced by endogenous and exogenous catecholamine stimulation of beta receptors.
VISKAZIDE should be administered with caution to patients with allergic rhinitis prone to bronchospasm.
Acute Respiratory Toxicity
Very rare severe cases of acute respiratory toxicity, including acute respiratory distress syndrome (ARDS) have been reported after taking hydrochlorothiazide. Pulmonary edema typically develops within minutes to hours after hydrochlorothiazide intake. At the onset, symptoms include dyspnea, fever, pulmonary deterioration and hypotension. Hydrochlorothiazide should not be administered to patients who previously experienced ARDS following hydrochlorothiazide intake.
Sensitivity/Resistance
Photosensitivity reactions have been reported with the use of thiazide diuretics. If photosensitivity reactions occur during treatment with hydrochlorothiazide-containing drugs, treatment should be stopped.
Skin
Various skin rashes and conjunctival xerosis have been reported with beta blockers, including pindolol. A severe syndrome (oculo-muco-cutaneous syndrome) whose signs include conjunctivitis sicca and psoriasiform rashes, otitis, and sclerosing serositis has occurred with the chronic use of one beta-adrenergic blocking agent (practolol). This syndrome has not been observed with pindolol, however, physicians should be alert to the possibility of such reactions and should discontinue treatment with VISKAZIDE in the event that they occur. A switch to another therapeutic agent might be advisable.
Psoriasis
Since beta-blockers may aggravate psoriasis, VISKAZIDE should only be prescribed after careful consideration of benefits and risks in patients with history of psoriasis.
Photosensitivity
Photosensitivity reactions have been reported with the use of thiazide diuretics. If photosensitivity reactions occur during treatment with hydrochlorothiazide-containing drugs, treatment should be stopped.
7.1. Special Populations
7.1.1. Pregnancy
Thiazides cross the placental barrier and appear in cord blood. The use of VISKAZIDE in pregnancy or in women of child-bearing potential requires that the anticipated benefit be weighed against possible risk to mother and/or fetus. These hazards include fetal or neonatal jaundice, thrombocytopenia, and possibly, other adverse reactions which have occurred in the adult.
7.1.2. Breastfeeding
Thiazides appear in human milk. If use of VISKAZIDE is deemed essential, the patient should stop nursing.
7.1.3. Pediatrics (< 18 years of age)
No data are available to Health Canada; therefore, Health Canada has not authorized an indication for pediatric use.
7.1.4. Geriatrics (> 65 years of age)
No evidence exists that geriatric patients require different dosages of pindolol; however, these patients should be treated cautiously. An excessive decrease in blood pressure or pulse rate may reduce blood supply to vital organs to inadequate levels.
8. Adverse Reactions
8.1. Adverse Reaction Overview
Adverse reactions that have been reported with the individual components are listed below:
Cardiovascular
Congestive heart failure (See 7. Warnings and Precautions), severe bradycardia (See 7. Warnings and Precautions) may occur as may syncope, light-headedness, and postural hypotension. Lengthening of PR interval, second degree AV block, palpitation, chest pains, cold extremities, Raynaud's phenomenon, claudication, hot flushes, very rarely arrhythmia, coronary insufficiency. Orthostatic hypotension may be potentiated by alcohol, barbiturates or narcotics.
Central Nervous System
Insomnia, nightmares, vivid dreams, fatigue, drowsiness, weakness, paresthesias, dizziness, vertigo, tinnitus, headache, mental depression, nervousness. Rarely have the following adverse reactions been reported: aggressiveness, motor disorders, confusion, xanthopsia.
Gastrointestinal
Anorexia, gastric irritation, cramping, diarrhea, constipation, flatulence, heartburn, nausea and vomiting, abdominal pain, dry mouth, jaundice (intrahepatic, cholestatic), pancreatitis, sialadenitis.
Respiratory
Shortness of breath and/or dyspnea, wheezing, bronchospasm (See 2. Contraindications and 7. Warnings and Precautions).
Hematologic
Leukopenia, agranulocytosis, thrombocytopenia, aplastic anemia, hemolytic anemia.
Urogenital
Impotence.
Hypersensitivity
Exanthema, sweating, pruritis, purpura, photosensitivity, urticaria, exfoliative dermatitis, psoriasiform rash, necrotizing angiitis vasculitis, cutaneous vasculitis, fever, respiratory distress, including pneumonitis, anaphylactic reactions.
Special Senses
Visual disturbances, including xanthopsia and transient blurred vision, dry eyes, conjunctivitis, itching eyes and/or burning of the eyes, tinnitus, vestibular disorder.
Other
Hyperglycemia, glycosuria, hyperuricemia, muscle cramps, weakness, restlessness, weight gain or loss, urinary frequency, appetite stimulation.
8.4. Abnormal Laboratory Findings: Hematologic, Clinical Chemistry, and Other Quantitative Data
Clinical Trial Findings
On rare occasions, changes in the following parameters were noted: elevations in transaminases, alkaline phosphatase, LDH, serum uric acid; a reduction in bilirubin. The most common changes associated with the thiazide component are increases in uric acid and decreases in serum potassium and chloride.
8.5. Post-Market Adverse Reactions
These adverse drug reactions (Table 2) have been derived from post-marketing experience with pindolol. Because these reactions are reported voluntarily from a population of uncertain size, it is not possible to reliably estimate their frequency which is therefore categorized as not known. Adverse drug reactions are listed according to system organ classes in MedDRA. Within each system organ class, ADRs are presented in order of decreasing seriousness.
Table 2 – Adverse drug reactions (frequency not known)
| System Organ Class | Adverse Drug Reaction |
|---|---|
| Psychiatric disorders | Sleep disorders, depression, hallucinations |
| Nervous system disorders | Tremor, dizziness, headache |
| Cardiac disorders | Bradycardia, conduction disorder, cardiac failure |
| Vascular disorders | Hypotension, symptoms of peripheral vascular disorders (peripheral coldness), Raynaud’s-like symptoms |
| Respiratory, thoracic and mediastinal disorders | Bronchospasm, dyspnea |
| Gastrointestinal disorders | Gastrointestinal disorders (nausea, vomiting, abdominal pain and diarrhea) |
| Skin and subcutaneous tissue disorders | Skin reaction, hyperhidrosis, worsening of psoriasis |
| Musculoskeletal and connective tissue disorders | Muscle cramps |
| General disorders and administration site conditions | Fatigue |
Non-melanoma skin cancer
Some pharmacoepidemiological studies have suggested a higher risk of squamous cell carcinoma (SCC) and basal cell carcinoma (BCC) of the skin with increasing use of hydrochlorothiazide. A systematic review and meta-analysis undertaken by Health Canada suggested that, with important uncertainty, the use of hydrochlorothiazide for several years (>3 years) could lead to:
- 122 additional cases (95% CI, from 112 to 133 additional cases) of SCC per 1000 treated patients compared with non-use of hydrochlorothiazide (meta-analysis of 3 observational studies);
- 31 additional cases (95% CI, from 24 to 37 additional cases) of BCC per 1000 treated patients compared with non-use of hydrochlorothiazide (meta-analysis of 2 observational studies).
- Acute respiratory distress syndrome (ARDS) (very rare).
- Eye disorders - choroidal effusion, acute myopia, acute angle-closure glaucoma (frequency unknown).
9. Drug Interactions
9.4. Drug-Drug Interactions
The drugs listed in table 3 are based on either drug interaction case reports or studies, or potential interactions due to the expected magnitude and seriousness of the interaction (i.e., those identified as contraindicated).
Table 3 – Established or Potential Drug-Drug Interactions for Pindolol
| [Non-proprietary name(s) of the drug product(s)] | Source of evidence | Effect | Clinical comment |
| Monoamine oxidase (MAO) inhibitors | C, T | Combining these medications may increase the risk of hypotension, orthostasis, bradycardia, and heart failure due to excessive reduction of sympathetic activity. Possibly significant hypertension may theoretically occur up to 14 days following discontinuation of the MAO inhibitor. | Monoamine oxidase (MAO) inhibitors may potentiate the pharmacologic effects of beta-blockers, which are thought to competitively antagonize catecholamines at cardiac and other peripheral adrenergic neurons. Concurrent use with beta-blockers is not recommended. |
| Antidiabetic agents | T | Beta-blockers may interfere with the usual hemodynamic response to hyperglycaemia and produce a rise in blood pressure associated with severe bradycardia. | Beta-blockade reduces the release of insulin in response to hyperglycemia; therefore, it may be necessary to adjust the dose of antidiabetic drugs. Beta-blockers should be avoided in unstable diabetic patients (patients who experience wide and unpredictable fluctuations of blood glucose values and/or difficulty in stabilizing blood glucose levels) prone to episodes of hypoglycemia (see 7. Warnings and Precautions). |
| Calcium-channel blocking agents | CT (Carruthe rs 1991) | because of their potential effect on the cardiac conduction system and contractility, the i.v. route must be avoided. Oral treatment, if judged absolutely necessary, requires careful monitoring, especially when the beta-blocker is combined with a verapamil-type calcium antagonist. | Severe reduction in blood pressure and heart failure upon the concomitant administration of dihydropyridine derivatives such as nifedipine with pindolol in patients with latent cardiac insufficiency is possible. |
| Anti-adrenergic agents | T | Antihypertensive effect of alpha-adrenergic blockers such as guanethidine, betanidine, reserpine, alpha-methyldopa or clonidine may be potentiated by beta-blockers, which may lead to postural hypotension. | When therapy is discontinued in patients receiving a beta-blocker and clonidine concurrently, the beta-blockers should be gradually discontinued several days before clonidine is discontinued, in order to reduce the potential risk of a clonidine withdrawal hypertensive crisis (rebound effect). Monitoring of blood pressure is recommended during the anti-adrenergics withdrawal. |
| Non-steroidal anti-inflammatory drugs (NSAIDs) | T | Concomitant administration of non-steroidal anti-inflammatory drugs including COX-2 inhibitors with a beta-blocker, may decrease its antihypertensive effect, possibly as a result of the inhibition of renal prostaglandin synthesis and sodium and fluid retention caused by NSAIDs. | Anti-hypertensive effects of beta-blockers may be decreased by non-steroidal anti-inflammatory drugs, which may lead to uncontrolled hypertension. Monitoring is required. |
| Phenothiazines | CT | Concurrent administration of pindolol and thioridazine is reported to result in a moderate increase in the serum levels of thioridazine and two of its metabolites, as well as higher than expected serum pindolol levelS. | Concurrent use with beta-blockers with phenothiazines results in an increased plasma concentration of either drug, which may lead to hypotension, ventricular tachycardia, and pigmentary retinopathy. Monitoring is required. |
| Sympathomimetic drugs | T | Concomitant administration of sympathomimetic drugs such as adrenaline, noradrenaline, isoprenaline, ephedrine, phenylephrine phenylpropanolamine, or xanthine derivatives with a non-selective beta-blocker may enhance the pressor response resulting in severe hypertension due to antagonistic effects. | Pindolol may antagonize the effects of sympathomimetic drugs and xanthine derivatives which may lead to severe hypertension. Monitoring is required. |
| Anesthetic agents | CT | Beta-blockers and certain anaesthetics may be additive in their cardio-depressant effect and may lead to protracted severe hypotension (see 7. Warnings and Precautions). | Anaesthetic agents causing myocardial depression, such as cyclopropane and trichloroethylene, are best be avoided. |
| Anti-arrhythmic agents | CT | Concomitant administration of beta-blockers with class I anti-arrhythmic agents such as disopyramide, tocainide, flecainide or amiodarone have a potentiating effect on atrial-conduction time and induce negative inotropic effect, which may lead to myocardial depression, cardiac failure, hypotension, bradycardia, AV block and asystole. | Although this potentiation effect is weak for pindolol, the possibility of interactions with anti-arrhythmic agents can not be eliminated. Monitoring is required. |
| Digitalis glycosides | T | Beta-blockers and digitalis glycosides may be additive in their depressant effect on myocardial conduction, particularly through the atrioventricular node. | Concomitant administration of digitalis glycosides may induce serious bradycardia or heart block and thus should be avoided. |
| Ergot alkaloid | T | Administration with beta-blockers may enhance the vasoconstrictive effect of ergot alkaloids. | Concomitant administration with beta-blockers with ergot alkaloid may enhance the vasoconstriction, which leads to hypertension. |
| Cimetidine | CT | Cimetidine is a moderate inhibitor of multiple cytochrome enzymes such as CYP2D6, CYP3A4, CYP2C19, CYP2E1, CYP2C9, and CYP1A2. Concomitant administration of cimetidine may inhibit the hepatic metabolism of pindolol resulting in increased plasma concentrations of pindolol, which may lead to hypotension. | Monitoring is required. |
| Fingolimod | CT | Bradycardia | Concomitant use of fingolimod with beta blockers may potentiate bradycardic effects and is not recommended. Where such coadministration is considered necessary, appropriate monitoring at treatment initiation, i.e. at least overnight monitoring, is recommended. |
Legend: C = Case Study; CT = Clinical Trial; T = Theoretical; PBPK = Physiologically based pharmacokinetic modeling; popPK = Population pharmacokinetic modeling
Table 4 – Established or Potential Drug-Drug Interactions for Hydrochlorothiazide
| [Non-proprietary name(s) of the drug product(s)] | Source of evidence | Effect | Clinical comment |
|---|---|---|---|
| Alcohol, barbiturates, or narcotics | C | Potentiation of orthostatic hypotension may occur. | Avoid alcohol, barbiturates or narcotics, especially with initiation of therapy. |
| Amphotericin B | T | Amphotericin B increases the risk of hypokalemia induced by thiazide diuretics | Monitor serum potassium level. |
| Antidiabetic agents (e.g. insulin and oral hypoglycemic agents) | CT | Thiazide-induced hyperglycemia may compromise blood sugar control. Depletion of serum potassium augments glucose intolerance. | Monitor glycemic control, supplement potassium, if necessary, to maintain appropriate serum potassium levels, and adjust diabetes medications as required. |
| Antihypertensive drugs | CT | Hydrochlorothiazide may potentiate the action of other antihypertensive drugs (e.g. guanethidine, methyldopa, beta-blockers, vasodilators, calcium channel blockers, ACEI, ARB, and direct renin inhibitors). | |
| Antineoplastic drugs, including cyclophosphamide and methotrexate | C | Concomitant use of thiazide diuretics may reduce renal excretion of cytotoxic agents and enhance their myelosuppressive effects. | Hematological status should be closely monitored in patients receiving this combination. Dose adjustment of cytotoxic agents may be required. |
| Bile acid sequestrants, eg. cholestyramine | CT | Bile acid sequestrants bind thiazide diuretics in the gut and impair gastrointestinal absorption by 43- | Give thiazide 2-4 hours before or 6 hours after the bile acid sequestrant. Maintain a consistent sequence of |
| 85%. Administration of thiazide 4 hours after a bile acid sequestrant reduced absorption of hydrochlorothaizide by 30-35%. | administration. Monitor blood pressure, and increase dose of thiazide, if necessary. | ||
| Calcium and vitamin D supplements | C | Thiazides decrease renal excretion of calcium and increase calcium release from bone. | Monitor serum calcium, especially with concomitant use of high doses of calcium supplements. Dose reduction or withdrawal of calcium and/or vitamin D supplements may be necessary. |
| Carbamazepine | C | Carbamazepine may cause clinically significant hyponatremia. Concomitant use with thiazide diuretics may potentiate hyponatremia. | Monitor serum sodium levels. Use with caution. |
| Corticosteroids, and adrenocorticotropic hormone (ACTH) | T | Intensified electrolyte depletion, particularly hypokalemia, may occur. | Monitor serum potassium, and adjust medications, as required. |
| Digoxin | CT | Thiazide-induced electrolyte disturbances, i.e. hypokalemia, hypomagnesemia, increase the risk of digoxin toxicity, which may lead to fatal arrhythmic events. | Concomitant administration of hydrochlorothiazide and digoxin requires caution. Monitor electrolytes and digoxin levels closely. Supplement potassium or adjust doses of digoxin or thiazide, as required. |
| Drugs that alter GI motility, i.e., anti-cholinergic agents, such as atropine and prokinetic agents, such as metoclopramide, domperidone | CT, T | Bioavailability of thiazide diuretics may be increased by anticholinergic agents due to a decrease in gastrointestinal motility and gastric emptying. Conversely, prokinetic drugs may decrease the bioavailability of thiazide diuretics. | Dose adjustment of thiazide may be required. |
| Gout medications (allopurinol, uricosurics, xanthine oxidase inhibitors) | T, RSC | Thiazide-induced hyperuricemia may compromise control of gout by allopurinol and probenecid. The co-administration of hydrochlorothiazide and allopurinol may increase the incidence of hypersensitivity reactions to allopurinol. | Dosage adjustment of gout medications may be required. |
| Lithium | CT | Thiazide diuretics reduce the renal clearance of lithium and add a high | Concomitant use of thiazide diuretics with lithium is generally not |
| risk of lithium toxicity. | recommended. If such use is deemed necessary, reduce lithium dose by 50% and monitor lithium levels closely. | ||
| Nonsteroidal anti-inflammatory drugs (NSAID) | CT | NSAID-related retention of sodium and water antagonises the diuretic and antihypertensive effects of thiazides. NSAID-induced inhibition of renal prostaglandins leading to decreases of renal blood flow, along with thiazide-induced decreases in GFR may lead to acute renal failure. Patients with heart failure may be at particular risk. | If combination use is necessary, monitor renal function, serum potassium, and blood pressure closely. Dose adjustments may be required. |
| Selective serotonin reuptake inhibitors (SSRIs, e.g. citalopram, escitalopram, sertraline) | T, C | Concomitant use with thiazide diuretics may potentiate hyponatremia. | Monitor serum sodium levels. Use with caution. |
| Skeletal muscle relaxants of the curare family, eg., tubocurare | C | Thiazide drugs may increase the responsiveness of some skeletal muscle relaxants, such as curare derivatives | |
| Topiramate | CT | Additive hypokalemia. Possible thiazide-induced increase in topiramate serum concentrations. | Monitor serum potassium and topiramate levels. Use potassium supplements, or adjust topiramate dose as necessary. |
9.5. Drug-Food Interactions
Interactions with food have not been established.
9.6. Drug-Herb Interactions
Interactions with herbal products have not been established.
9.7. Drug-Laboratory Test Interactions
Interactions with laboratory tests have not been established.
10. Clinical Pharmacology
10.1. Mechanism of Action
VISKAZIDE combines the antihypertensive activity of two agents: a beta-adrenergic receptor-blocking agent (pindolol) and a diuretic (hydrochlorothiazide).
Pindolol is a non-selective beta-adrenergic receptor blocking agent which possesses partial agonist activity (intrinsic sympathomimetic activity - I.S.A.).
The mechanism of the antihypertensive effect of beta-adrenergic receptor-blocking agents has not been established. Among the factors that may be involved are:
- a) competitive ability to antagonize catecholamine induced tachycardia at the beta-receptor sites in the heart, thus decreasing cardiac output,
- b) a reduction in total peripheral resistance,
- c) inhibition of the vasomotor centres,
- d) inhibition of renin release by the kidneys.
Pindolol
Pindolol possesses partial agonist (intrinsic sympathomimetic) activity.
Pindolol decreases the basal rate of myocardial oxygen consumption and blocks increases mediated by increased sympathetic nervous system activity.
Pindolol has antiarrhythmic activity. Pindolol has been reported to reduce plasma renin activity in some patients. However, plasma renin may remain unchanged or increase following treatment. There does not appear to be any significant relationship between the antihypertensive activity of pindolol and changes in plasma renin activity.
Hydrochlorothiazide
Hydrochlorothiazide has diuretic and antihypertensive activities. This compound increases the excretion of sodium and chloride in approximately equivalent amounts and causes a simultaneous, usually minimal loss of bicarbonate. The excretion of ammonia is reduced slightly by hydrochlorothiazide and the blood ammonia concentration may be increased. The excretion of potassium is increased slightly. Calcium excretion is decreased by hydrochlorothiazide and magnesium excretion is increased.
10.2. Pharmacodynamics
Hydrochlorothiazide increases excretion of sodium and chloride in approximately equivalent amounts, and may cause a simultaneous, usually minimal, loss of bicarbonate. Natriuresis is usually accompanied by some loss of potassium. The mechanism of the antihypertensive effect of thiazides may be related to the excretion and redistribution of body sodium. Hydrochlorothiazide usually does not decrease normal blood pressure.
The combination of pindolol with thiazide-like diuretics has been shown to be compatible and generally more effective than either of the drugs used alone in reducing elevated blood pressure.
Hydrochlorothiazide
The onset of the diuretic action of hydrochlorothiazide occurs in two (2) hours and the peak action in about four (4) hours. Diuretic activity lasts about six (6) to twelve (12) hours.
Pindolol
Effects on the Cardiovascular System
Pindolol in the non-anesthetized dog, at a dose of 0.05 mg/kg i.v. , produced a 70% inhibition of tachycardia and changes in blood pressure induced by isoproterenol at doses of 2 mg/kg i.v. Complete antagonism was observed following pindolol at doses of 0.1 to 5 mg/kg i.v. In the anesthetized dog, 0.2 to 2.0 mg/kg i.v. produced dose dependent decreases in blood pressure; heart rate changes were unrelated to dose and were reduced by 12% after a dose of 0.2 mg/kg i.v. and 4% after i.v. injection of 2 mg/kg.
In the anesthetized dog, 0. 2 to 1 mg/kg i.a. antagonized the vasodilation induced by isoproterenol, whereas transient 25 to 40% reductions in vascular resistance were observed after intra-arterial doses of 50 to 200 mg/kg. Intravenous doses of 2 mg/kg of pindolol in this preparation, elicited peripheral vasodilation and an associated reduction in total peripheral resistance.
In vivo, studies on the guinea pig atrium showed that pindolol produced dose dependent antagonism of epinephrine-induced positive inotropy and chronotropy.
In five healthy volunteers given a single oral dose of 10 mg of Pindolol, antagonism of isoproterenol-induced tachycardia and changes in blood pressure and heart rate were observed 30 minutes after ingestion and persisted for 24 hours.
In ten hypertensive patients receiving pindolol for 16 months in divided doses of 20 to 40 mg, blood pressure reduction was associated with statistically significant reduction in forearm and total systemic vascular resistance at rest and during stress testing. Venous tone was significantly reduced during and after exercise. No significant change was reported in cardiac output following prolonged use (see 10. Clinical Pharmacology; 10.1. Mechanism of Action).
Pindolol has little membrane stabilizing activity being approximately 1/12 that of quinidine in prolonging the relative refractory period of cardiac cells in the isolated guinea pig atrium. A concentration of up to 5% pindolol was devoid of local anesthetic effects when applied to the cornea of the eye.
Long-lasting increases in myocardial activity manifested by positive chronotropic actions were observed following i.v. infusions of pindolol at doses of 0.16 mcg/kg to 2.5 mg/kg in the reserpinized, adrenalectomized and vagotomized cats.
At doses of 8 mg/kg in the anesthetized dog, pindolol decreased the dose of ouabain required to produce ventricular arrhythmia. In guinea pigs and dogs, it delayed the onset of ouabain-induced ventricular arrhythmia and in the dog produced reversion to sinus rhythm.
Effects on Pulmonary Function
In a study of 58 hypertensive patients with normal respiratory function who received oral doses of 15, 30, or 60 mg of pindolol, no significant changes were observed in forced expiratory volume, maximum voluntary ventilation rate, maximum expiratory flow rate and maximum mid-expiratory flow rate.
Decreased FEV1 has, however, been reported in other studies.
Other Effects
Electroencephalographic changes, following oral doses of 5 and 10 mg in healthy volunteers, consisted of theta and fast beta and decreases in alpha activity. In rats given 5.2 mg/kg s.c., pindolol blocked tetrabenazine induced ptosis but not catalepsy. In mice at doses of 1 to 30 mg/kg i.v., pindolol antagonized reserpine-induced hypothermia
10.3. Pharmacokinetics
Hydrochlorothiazide
Hydrochlorothiazide is eliminated rapidly by the kidney. Its rate of elimination is decreased somewhat by the coadministration of probenecid without, however, an accompanying reduction in diuresis.
Pindolol
Absorption
In man, orally-administered pindolol is rapidly and almost completely absorbed (≥95%) from the gastrointestinal tract. The mean absolute bioavailability after oral administration is about 87-92%. Plasma levels of 10 to 30 ng/mL are associated with its therapeutic efficacy. Following single dose administration 5 mg pindolol, the mean maximum plasma concentration (Cmax) of pindolol was 33.1 ± 5.2 ng/mL (Tmax 1-2 h).
Distribution
Approximately, 40% of pindolol is bound to plasma proteins. Pindolol is extensively and rapidly distributed throughout the body with a mean volume of distribution of 2-3 L/kg.
Metabolism
Pindolol is partially metabolized in the liver with approximately 30 to 40% of an oral dose being excreted unchanged in the urine. The remaining 60 to 70% of pindolol is metabolized in the liver forming inactive metabolites - hydroxylate, which is excreted via kidney and liver as glucuronides and ethereal sulfate.
Elimination
The elimination rate of pindolol is not dose dependent. The elimination half-life of pindolol is 3 to 4 hours and the drug has a systemic clearance of between 400 and 500 mL/min. The elimination kinetics has generally been described as a mono-exponential decay function using one compartment pharmacokinetics. The inactive polar metabolites are excreted out with elimination half-life of 8 h. The fraction eliminated in bile is approximately 6-8%. Approximately 80% of an oral dose is accounted for in the urine within 24 hours.
Special populations and conditions
- Geriatrics: The elderly population may show higher plasma concentrations of pindolol as a combined result of a decreased metabolism of the drug in elderly population, a decreased hepatic blood flow and a decreased renal elimination.
Pregnancy and breastfeeding: The elimination half-life of pindolol does not differ significantly between pregnant and non-pregnant patients (See 7. Warnings and Precautions). Transplacental distribution of pindolol is not stereoselective. Pregnancy may alter the
- pharmacokinetic disposition of pindolol, suggesting an increase in the distribution volume and total clearance.
- Hepatic Insufficiency: Patients with impaired renal or hepatic function may usually be treated with normal doses. Only in severe cases may a reduction of the daily dose be necessary. The plasma half-life of pindolol is increased up to 30 hours, depending on severity, in patients with liver cirrhosis.
- Renal Insufficiency: Patients with impaired renal or hepatic function may usually be treated with normal doses. Only in severe cases may a reduction of the daily dose be necessary. The plasma half-life of pindolol is increased up to 11.5 hours, depending on severity, in patient with renal impairment.
- Storage, Stability, and Disposal
Store in the original package, protect from light. Do not use after the expiry date shown on the box.
Part 2: Scientific Information
13. Pharmaceutical Information
Drug Substance
Non-proprietary name of the drug substance(s): Pindolol
Chemical name: 4-(2-hydroxy-3-iso-propyl-aminopropoxy)-indole
Molecular formula and molecular mass: C14H20N2O2, 248.3
Structural formula:
NH O NH OH CH3 CH3 *
Physicochemical properties: Visken is the free base of pindolol. It is a white, odourless powder, soluble in methanol and acetic acid.
Drug Substance
Non-proprietary name of the drug substance(s): Hydrochlorothiazide
Chemical name: 6-chloro-3, 4-di-hydro-2H-1,2,4-benzothiadiazine-7-sulfonamide 1, 1-dioxyde
Molecular formula and molecular mass: C7H8C1N3O4S2, 297.73
Structural formula:
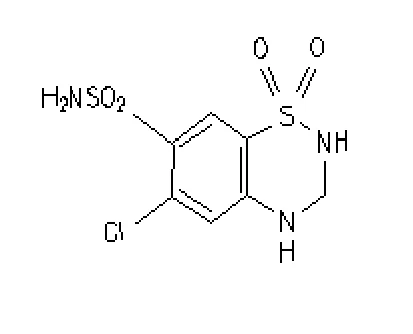
Physicochemical properties: Hydrochlorothiazide is a white or practically white crystalline compound with low solubility in water, but is readily soluble in dilute aqueous sodium hydroxide.
16. Non-Clinical Toxicology
General toxicology:
Deposition of Pigment
Oral administration of pindolol to rats at a dose of 200 mg/kg/day for 26 weeks resulted in the deposition of a melanin-like pigment in the liver, spleen, adrenal gland and subcutaneous tissue. Partial disappearance of this pigment from Kupffer cells in the liver occurred within four weeks following discontinuation of pindolol.
In dogs given oral doses of 5, 15, and 45 mg/kg/day for 26 weeks, dose related increases in hepatocyte lipid content were observed.
The deposition of pigment and increased hepatocyte lipid content were recorded. However, all tests done for hepatic, splenic and adrenal function were normal and the significance of pigment and lipid changes is unknown.
Toxicity
| Oral LD50 (mg/kg) | ||
| Species | Pindolol | Hydrochlorothiazide |
| Mice | 200 | ≥ 10,000 |
| Rat | 260 | ≥ 10,000 |
SUBACUTE TOXICITY
Pindolol
| Species | Strain | Sex M/F | Number of groups | Number of Animals per Group | Dose mg/kg/day | Route | Duration of Study | Toxic Effects |
| Rats | 60/60 | 3 | 10 M 10 F | 0, 16, 66, 246 | P.O. | 13 W | At 246 mg/kg there was a mortality rate of 20%. Arrest of spermatogenesis in males and hypoplastic uteri in females were observed at doses of 66 and 246 mg/kg. Doses of 16, 66 and 246 mg/kg slightly to moderately increased SGPT levels, and reduced food intake, the efficiency of food utilization and organ and body weights. Treated animals had a slightly higher incidence of infection than controls. Granular inclusions in liver and adrenal cells and increased numbers of fat droplets in renal tubule cells were seen at doses of 246 mg/kg. Similar but less prominent changes were found at 66 mg/kg. There were isolated incidences of thymus involution, contraction of the seminal vesicles and prostatic atrophy. Green discoloration of the urine was observed. | |
| Rats | 40/40 | 4 | 10 M 10 F | 1.7; 5, 25, 130 | P.O. | 26 W | At 130 mg/kg/day decreased body weight and cyanosis were observed. | |
| Dogs | Beagle | 6/6 | 3 | 2 M 2 F | 5, 20, 80 | P.O. | 13 W | At 80 mg/kg/day convulsions, gastrointestinal disturbances, mydriasis, erythema secondary to cutaneous vasodilation were observed. Food intake and body weight were reduced. |
SUBACUTE TOXICITY
Pindolol (cont.)
| Species | Strain | Sex M/F | Number of groups | Number of Animals per Group | Dose mg/kg/da y | Route | Duration of Study | Toxic Effects |
| Dogs | Beagle | 12/12 | 4 | 3 M 3 F | 0, 5, 15, 45 | P.O. | 26 W | At 45 mg/kg the mortality rate was 50%. Hepatocyte swelling, and the presence of intracellular hyaline droplets and lipochrome pigment in hepatocytes and Kupffer cells were seen at 15 and 45 mg/kg and a few single sporadic degenerating liver cells were observed. Green discolouration of the urine was seen at 15 and 45 mg/kg/day. 1 dog in each group given 5, 15, and 45 mg/kg/day showed transient increases in alkaline phosphatase. In the 45 mg/kg/day group, convulsions, gastrointestinal disturbances, arrest of spermatogenesis, weight loss and reduced adreno-cortical lipids were observed. |
| Rats | 30/30 | 3 | 10 M 10 F | 0, 1, 3 | I.V. | 4 W | None | |
| Rats | 5/5 | 1 | 5 M 5 F | 0 | I.M. | 4 W | _ _ _ _ | |
| 10/10 | 1 | 10 M 10 F | 5 | I.M. | 4 W | Slight irritant effect at injection site. |
CHRONIC TOXICITY
Pindolol
| Species | Strain | Sex M/F | Number of groups | Number of Animals per Group | Dose mg/kg/day | Route | Duration of Study | Toxic Effects |
| Rats | 120/120 | 4 | 30 M 30 F | 0, 2, 14, 98 | P.O. | 2 Y | Green discolouration of the urine at 98 mg/kg. At 2, 14 and 98 mg/kg deposition of a greenish brown pigment in Kupffer cells of the liver. | |
| Dogs | Beagle | 4/4 | 4 | 4 M 4 F | 0, 2, 6, 8 | P.O. | 2 Y | Tachycardia of 1 week duration. Erythema secondary to cutaneous vasodilatation which was not dose dependent. Emesis and soft stools. |
| Dogs | Beagle | 2/2 | 1 | 4 | 0 | I.V. | 4 W | _ _ _ _ |
| 4/4 | 2 | 5 | 1.5 | I.V. | 4 W | Erythema secondary to cutaneous vasodilation. | ||
| Monkeys | Rhesus | 9/9 | 3 | 3 M 3 F | 0, 2.5, 25 | P.O. | 1 Y | At 2.5 mg/kg heart rate was slowed 15 to 20%. Bradycardia was seen at 25 mg/kg. Green discolouration of the urine at 25 mg/kg. |
Carcinogenicity:
Carcinogenicity Studies (pindolol)
Pindolol was administered to 50 male and 50 female mice (Sandoz OF1 Strain) at dietary levels of approximately 124 mg/kg/day for 82 weeks, with an equal number of mice serving as controls. The incidence of nodules and masses observed at necropsy were comparable in the treated and control groups. This strain of mice was previously shown to be susceptible to chemical carcinogenesis.
Pindolol was given to 50 male and 50 female rats (Sandoz OFA Strain) at a mean dose of 50 mg/kg/day for 83 weeks. A similar group of 100 rats served as a control. Mortality and incidence of tumor were comparable in the treated and untreated groups. This strain of rat was previously shown to be susceptible to 2AAF chemically induced carcinogenesis.
Hydrochlorothiazide
In dogs given doses of 250, 500 and 1000 mg/kg seven days a week for eight weeks, no gross signs of drug effect were noted except for electrolyte imbalance.
Chronic oral toxicity studies in the rat using doses of up to 2000 mg/kg/day five days per week for 26 weeks showed no signs of drug effect and no drug related changes on post mortem examination. In dogs, oral doses of 0, 125, 250 mg/kg/day five days per week for 26 weeks; 500 mg/kg/day for seven weeks; 11 weeks without drug then 500 mg/kg/day seven days per week for eight weeks were given. Slight depression of plasma potassium, small amounts of yellow crystalline precipitate in the bladder in two of twelve dogs were found on gross examination. Histomorphologic studies did not show drug related changes.
According to the experimental data available, hydrochlorothiazide revealed inconsistent evidence of carcinogenic activity in rats and mice, with conflicting evidence of hepatic adenoma in male mice at the highest dose and adrenal pheochromocytoma in one rat study but not in another. Current evidence is inadequate to draw a clear conclusion for a carcinogenic effect of hydrochlorothiazide in animals.
The mutagenic potential was assessed in a series of in vitro and in vivo test systems. While some positive results were obtained in vitro, all in vivo studies provided negative results.
Hydrochlorothiazide enhanced the UVA-induced formation of pyrimidine dimers in vitro and in the skin of mice following oral treatment. It is therefore concluded that although there is no relevant mutagenic potential in vivo, hydrochlorothiazide could enhance the genotoxic effects of UVA light. This mechanism of photosensitization could be associated with a higher risk for nonmelanoma skin cancer.
Reproductive and developmental toxicology:
Teratology and Reproduction Studies (pindolol)
Rat: (Sandoz Closed Strain). Doses of 30 and 100 mg/kg were administered orally to groups of 20 pregnant rats on days 7-16 of gestation. Treatment with pindolol did not adversely affect any of the parameters studied.
The parameters studied in the rat and rabbit teratology studies were the following: Total number of pregnancies, implantations, viable fetuses, dead fetuses, total prenatal deaths, abnormal fetuses in % of living fetuses.
Rabbit: (Swiss Hare Strain). Doses of 8, 23 and 80 mg/kg were administered orally to groups of respec-tively 13, 16 and 15 pregnant rabbits on days 6-18 of gestation. None of the parameters studied was significantly affected.
Rat: (Sandoz Closed Strain). Doses of 10, 30 and 100 mg/kg were administered orally to groups of 15 male (Sandoz Closed Strain) and 30 female (Carworth Wistar CFE Strain) rats. Males were treated for 70 days prior to and during the mating period. The females were treated for up to 15 days prior to mating, during mating, and throughout the gestation and lactation period to 21 days postpartum, with an interim sacrifice at Day 13 of gestation. Spermatogenesis and fertility were reduced at doses of 30 but not 100 mg/kg/day. Tubular atrophy in the testes was found in male rats treated with doses of 30 and 100 mg/kg/day.
There was significantly greater mortality in the offspring of females treated with 100 mg/kg/day in the first four-day postpartum period and in pups of females receiving 30 mg/kg/day during the 4 to- 21-day postpartum interval. This increased mortality may be consequence of deficits in maternal rearing behaviour, inhibition of lactation or the presence of the drug in maternal milk.