


Product Monograph - Voranigo
Recent Major Label Changes
| 3 Serious Warnings and Precautions Box | 2026-05 |
|---|---|
| 7 Warnings and Precautions, Hepatic/Biliary/Pancreatic | 2026-05 |
| 7 Warnings and Precautions, Reproductive Health | 2026-05 |
| 7 Warnings and Precautions, 7.1.1 Pregnancy | 2026-05 |
Table of Contents
Recent Major Label Changes ................................................................................................... 2
Table of Contents ................................................................................................................... 2
Part 1: Healthcare Professional Information ........................................................................... 4
- 1.
Indications ....................................................................................................................... 4
1.1. Pediatrics .................................................................................................................. 4
1.2. Geriatrics .................................................................................................................. 4
- 2. Contraindications ............................................................................................................ 4
- 3. Serious Warnings and Precautions Box ............................................................................ 4
- 4.
Dosage and Administration ............................................................................................. 5
4.1. Dosing Considerations .............................................................................................. 5
4.2. Recommended Dose and Dosage Adjustment ......................................................... 5
4.4. Administration .......................................................................................................... 7
4.5. Missed Dose ............................................................................................................. 7
- 5. Overdose ......................................................................................................................... 7
- 6. Dosage Forms, Strengths, Composition, and Packaging ................................................... 8
- 7.
Warnings and Precautions ............................................................................................... 8
General ................................................................................................................................. 8
Hepatic/Biliary/Pancreatic .................................................................................................... 9
Monitoring and Laboratory Tests ......................................................................................... 9
Reproductive Health ............................................................................................................. 9
7.1. Special Populations ................................................................................................ 10
7.1.1. Pregnancy ...................................................................................................... 10
7.1.2. Breastfeeding ................................................................................................ 10
7.1.3. Pediatrics ....................................................................................................... 10
7.1.4. Geriatrics ....................................................................................................... 11
- 8.
Adverse Reactions ......................................................................................................... 11
8.1. Adverse Reaction Overview .................................................................................... 11
8.2. Clinical Trial Adverse Reactions .............................................................................. 11
8.2.1. Clinical Trial Adverse Reactions – Pediatrics .................................................. 12
8.3. Less Common Clinical Trial Adverse Reactions ....................................................... 12
8.3.1. Less Common Clinical Trial Adverse Reactions – Pediatrics ........................... 12
8.4. Abnormal Laboratory Findings: Hematologic, Clinical Chemistry, and Other Quantitative Data ............................................................................................................... 13
8.5. Post-Market Adverse Reactions ............................................................................. 13
- 9.
Drug Interactions ........................................................................................................... 14
9.4. Drug-Drug Interactions ........................................................................................... 14
9.5. Drug-Food Interactions........................................................................................... 15
9.6. Drug-Herb Interactions ........................................................................................... 16
9.7. Drug-Laboratory Test Interactions ......................................................................... 16
- 10.
Clinical Pharmacology ................................................................................................... 16
10.1. Mechanism of Action .............................................................................................. 16
10.2. Pharmacodynamics ................................................................................................ 16
10.3. Pharmacokinetics ................................................................................................... 16
- 11. Storage, Stability, and Disposal ...................................................................................... 18
Part 2: Scientific Information ................................................................................................ 19
- 13. Pharmaceutical Information .......................................................................................... 19
- 14.
Clinical Trials .................................................................................................................. 19
14.1. Clinical Trials by Indication ..................................................................................... 19
- 15. Microbiology ................................................................................................................. 22
- 16. Non-Clinical Toxicology .................................................................................................. 22
Patient Medication Information ........................................................................................... 24
Part 1: Healthcare Professional Information
1. Indications
VORANIGO (vorasidenib tablets) is indicated for:
the treatment of Grade 2a astrocytoma or oligodendroglioma with a susceptible isocitrate dehydrogenase-1 (IDH1) mutation or isocitrate dehydrogenase-2 (IDH2) mutation in adults and pediatric patients aged 12 years and older following surgical intervention.
Treatment with VORANIGO should be initiated following confirmation of an IDH1 or IDH2 mutation through a validated test.
a. World Health Organization (WHO) 2016, 2021 grading system
1.1. Pediatrics
Pediatrics (12 to 18 years): No patients under the age of 18 were treated with VORANIGO in the pivotal phase 3 study (INDIGO). Use of VORANIGO in pediatric patients 12 years and older is supported by evidence from studies in adults with additional population pharmacokinetic data demonstrating that age had no clinically meaningful effect on the pharmacokinetics of vorasidenib, that the exposure of vorasidenib is mostly similar between adults and pediatric patients age 12 years and older, and that the course of disease is sufficiently similar in adult and pediatric patients to allow extrapolation of data in adults to these pediatric patients. Pediatric patients may have a higher risk of adverse drug reactions (see 7 Warnings and precautions, 10.3 Pharmacokinetics, 14.1 Clinical Trials by Indication, and 4.2 Recommended Dose and Dosage Adjustment, Dosage Modifications).
The safety and efficacy of VORANIGO in children under 12 years of age have not been established. No data are available.
1.2. Geriatrics
Geriatrics (>65 years): No overall differences in safety or effectiveness were observed for patients aged 65 years or older (see 10.3 Pharmacokinetics, 14.1 Clinical Trials by Indication, and 4 Dosage and Administration).
2. Contraindications
VORANIGO is contraindicated in patients with:
- Hypersensitivity to the active substance or to any ingredient in the formulation, including any non-medicinal ingredient, or component of the container. For a complete listing, see 6 Dosage forms, strengths, composition and packaging.
3. Serious Warnings and Precautions Box
Hepatotoxicity (see 7 Warnings and Precautions, Hepatic/Biliary/Pancreatic).
4. Dosage and Administration
4.1. Dosing Considerations
Select patients for the treatment of Grade 2a astrocytoma or oligodendroglioma with VORANIGO based on the presence of IDH1 or IDH2 mutations in tumour specimens using an appropriate diagnostic test prior to initiation of treatment with VORANIGO.
a. WHO 2016, 2021 grading system
Assess complete blood counts and liver laboratory tests (aspartate aminotransferase (AST), alanine aminotransferase (ALT), gamma-glutamyl transferase (GGT), total bilirubin and alkaline phosphatase), prior to the initiation of VORANIGO, every 2 weeks during the first 2 months of treatment, then once monthly for the first 2 years of treatment and as clinically indicated thereafter, with more frequent testing in patients who develop transaminase elevations (see 7 Warnings and precautions, Hepatic/Biliary/Pancreatic).
Administer VORANIGO until radiographic or clinical disease progression or unacceptable toxicity.
4.2. Recommended Dose and Dosage Adjustment
The recommended dosage of VORANIGO in adults and pediatric patients 12 years and older:
- For patients weighing at least 40 kg, take 40 mg orally once daily.
- For patients weighing less than 40 kg, take 20 mg orally once daily.
Pediatric patients may have a higher risk of adverse drug reactions (see 7 Warnings and precautions, 10.3 Pharmacokinetics, 14.1 Clinical Trials by Indication, and 4.2 Recommended Dose and Dosage Adjustment, Dosage Modifications).
Dosage Modifications
Dose interruption or dose reduction may be required based on individual safety and tolerability. The recommended dose reduction levels are provided in Table 1.
The recommended management and dosage modifications for adverse reactions are provided in Table 2.
Table 2 − Recommended Dosage Modifications and Management for Adverse Reactions
| Table 1 − Recommended Dose Reductions for VORANIGO | |||||
|---|---|---|---|---|---|
| VORANIGO Dose level | Dose and schedule | Number and strength of tablets | |||
| Patients 12 years and older weighing at least 40 kg | |||||
| Starting dose | 40 mg once daily | One 40 mg tablet / once daily | |||
| First dose reduction | 20 mg once daily | Two 10 mg tablets / once daily | |||
| Second dose reduction | 10 mg once daily | One 10 mg tablet / once daily | |||
| Patients 12 years and older weighing less than 40 kg | |||||
| Starting dose | 20 mg once daily | Two 10 mg tablets / once daily | |||
| First dose reduction | 10 mg once daily | One 10 mg tablet / once daily | |||
| Permanently discontinue VORANIGO in patients unable to tolerate 10 mg once daily. | |||||
| Adverse Reaction | Severitya | Management and Dosage Modifications |
|---|---|---|
| Adverse Reaction | Severitya | Management and Dosage Modifications |
Hepatotoxicity (Elevation of ALT or AST) (see 7 Warnings and precautions) | Grade 1 ALT or AST increase >ULN to 3 x ULN without concurrent total bilirubin >2 x ULN | Continue VORANIGO at current dose. Monitor liver laboratory tests weekly until recovery to <Grade 1. |
Grade 2 ALT or AST >3 to 5 x ULN without concurrent total bilirubin >2 x ULN | First Occurrence: Withhold VORANIGO until recovery to ≤Grade 1 or baseline.
Recurrence: Withhold VORANIGO until recovery to ≤Grade 1 or baseline, and resume VORANIGO at reduced dose (see Table 1). | |
Grade 3 ALT or AST >5 to 20 x ULN without concurrent total bilirubin >2 x ULN | First Occurrence: Withhold VORANIGO until recovery to ≤Grade 1 or baseline.
Recurrence: Permanently discontinue VORANIGO. | |
Grade 2 or 3 Any ALT or AST >3 to 20 x ULN with concurrent total bilirubin >2 x ULN | First Occurrence: Withhold VORANIGO until recovery to ≤Grade 1 or baseline.
Recurrence: Permanently discontinue VORANIGO. | |
Grade 4 Any ALT or AST >20 x ULN | Permanently discontinue VORANIGO. | |
| Other Adverse Reactions | Grade 3 | First Occurrence: Withhold VORANIGO until recovery to ≤Grade 1 or baseline. |
| (see 8 Adverse reactions) |
Recurrence: Permanently discontinue VORANIGO. | |
| Grade 4 | Permanently discontinue VORANIGO. | |
Abbreviations: ALT = Alanine aminotransferase; AST = Aspartate aminotransferase; ULN = Upper limit of normal a Adverse reactions graded by the National Cancer Institute Common Terminology Criteria for Adverse Events (NCI-CTCAE) version 5.0.
Special Populations
Geriatrics (≥65 years of age)
No dose adjustment is recommended for patients ≥65 years of age (see 10.3 Pharmacokinetics).
Renal Impairment
No dosage adjustment is recommended for patients with renal impairment (creatinine clearance [CLcr] >40 mL/min estimated by Cockcroft-Gault). The pharmacokinetics and safety of vorasidenib have not been studied in patients with CLcr ≤40 mL/min or renal impairment requiring dialysis. VORANIGO should be used with caution in patients with CLcr ≤40 mL/min or who require dialysis (see 10.3 Pharmacokinetics).
Hepatic Impairment
No dosage adjustment is recommended for patients with mild or moderate (Child-Pugh Class A or B) hepatic impairment. The pharmacokinetics and safety of vorasidenib have not been studied in patients with severe hepatic impairment (Child-Pugh Class C). For patients with severe hepatic impairment, monitor for increased adverse reactions (see 10.3 Pharmacokinetics).
4.4. Administration
The tablets should be taken once daily at about the same time each day. Patients should not eat food at least 2 hours before and 1 hour after taking VORANIGO. The tablets are to be swallowed whole with a glass of water and should not be split, crushed or chewed to ensure the full dose is administered.
4.5. Missed Dose
If a dose is missed by less than 6 hours, take the missed dose as soon as possible. If a dose is missed by more than 6 hours, skip the missed dose, and take the next dose at the usual time.
If a dose is vomited, a replacement dose should not be taken. The dose should be taken as usual the following day.
5. Overdose
In the event of overdose, toxicity is likely to manifest as exacerbation of the adverse reactions associated with VORANIGO (see 8 Adverse reactions, 7 Warnings and precautions, and 4.2 Recommended Dose and Dosage Adjustment). There is no specific antidote for VORANIGO overdose.
For the most recent information in the management of a suspected drug overdose, contact your regional poison control centre or Health Canada’s toll-free number, 1-844 POISON-X (1-844-764-7669).
- 6. Dosage Forms, Strengths, Composition, and Packaging
Table 3 – Dosage Forms, Strengths, and Composition
*as vorasidenib hemicitric acid, hemihydrate
Description
VORANIGO is provided as film-coated tablets:
10 mg Film-coated Tablets
White to off-white, round, film-coated tablets, imprinted with ”10” in black ink on one side and plain on the other side.
40 mg Film-coated Tablets
White to off-white, oblong, film-coated tablets, imprinted with ”40” in black ink on one side and plain on the other side.
Sodium Content
The 10 mg or 40 mg film-coated tablets contain less than 1 mmol sodium (23 mg).
VORANIGO is supplied in a white high-density polyethylene (HDPE) bottle with a polypropylene child-resistant closure and polyethylene faced induction heat seal liner. Each bottle contains 30 film-coated tablets and a silica gel desiccant in 3 HDPE canisters.
7. Warnings and Precautions
General
Lactose
VORANIGO contains lactose. Patients with rare hereditary problems of galactose intolerance, total lactase deficiency or glucose-galactose malabsorption should not take this medicinal product.
| Route of Administration | Dosage Form/ Strength/Composition | Non-Medicinal Ingredients |
| oral | tablets 10 mg and 40 mg vorasidenib* | Croscarmellose sodium, hypromellose, lactose monohydrate, macrogol, magnesium stearate, microcrystalline cellulose, pharmaceutical ink, silicified microcrystalline cellulose, sodium lauryl sulfate, titanium dioxide |
Hepatic/Biliary/Pancreatic
In the INDIGO clinical trial (Study AG881-C-004), 36.5% (61/167) of patients treated with VORANIGO experienced ALT elevations of any grade and 24.6% (41/167) experienced AST elevations of any grade. Among these patients, 1.2% (2/167) had concurrent ALT or AST elevations >3 times the ULN and total bilirubin >2 times the ULN (see 8 Adverse reactions). Liver enzyme and bilirubin increases were transient and improved or resolved with dose modification or permanent discontinuation of treatment.
Drug-induced hepatotoxicity, including serious cases of hepatic failure, hepatic necrosis, autoimmune hepatitis and acute hepatitis have been observed in patients treated with VORANIGO in clinical studies and in the post market setting. Six patients and three patients met the laboratory criteria for Hy’s Law from clinical studies and the post market setting, respectively. In the clinical study setting, the median time-to-onset was 87 days (range: 45 – 243 days) and in the post-marketing setting, the median time-to-onset was 113 days (range: 91 – 117 days). Patients with Hy’s Law had concurrent elevations in ALT or AST >3 times the upper limit of normal and total bilirubin >2 times the upper limit of normal; these events were associated with cases of autoimmune hepatitis, DILI, hepatic necrosis and hepatic failure.
Monitor liver laboratory tests (ALT, AST, GGT, total bilirubin and alkaline phosphatase) prior to the start of VORANIGO, every 2 weeks during the first 2 months of treatment, then once monthly for the first 2 years, and as clinically indicated thereafter, with more frequent testing in patients who develop transaminase elevations. Weekly monitoring for ALT or AST elevations ≤3 times the ULN is recommended. Withhold, reduce dose or permanently discontinue VORANIGO based on the severity of the liver laboratory test abnormalities (see 4.2 Recommended Dose and Dosage Adjustment).
Monitoring and Laboratory Tests
Assess complete blood counts and liver laboratory tests (ALT, AST, GGT, total bilirubin and alkaline phosphatase) prior to the initiation of VORANIGO, every 2 weeks during the first 2 months of treatment, then once monthly for the first 2 years of treatment, and as clinically indicated thereafter, with more frequent testing in patients who develop transaminase elevations (see 7 Warnings and precautions, Hepatic/Biliary/Pancreatic). Manage any abnormalities in liver laboratory tests as outlined in Table 2.
Reproductive Health
Animal studies have shown that VORANIGO could cause reproductive harm and fetal toxicity when administered to pregnant women (see 16 Non-clinical toxicology and 7.1.1 Special Populations, Pregnancy).
Fertility
There are no human data on the effect of vorasidenib on fertility. No fertility studies in animals have been conducted to evaluate the effect of vorasidenib. Findings of adverse effects on reproductive organs in both sexes of rats were observed in repeat-dose studies with partial recovery noted (see 16 Non-clinical toxicology, Reproductive and Development Toxicology). The clinical relevance of these effects is unknown. Patients who are planning to conceive a child should be advised to seek reproductive counselling before starting treatment.
Contraception
Females
Women of childbearing potential should use effective non-hormonal contraception during treatment with VORANIGO and for at least 3 months after the last dose. Since the effect of vorasidenib on the metabolism and efficacy of systemically acting hormonal contraceptives has not been investigated, barrier methods should be applied as a second form of contraception to avoid pregnancy (see 9.4 Drug-Drug Interactions).
Males
Advise male patients with female partners of reproductive potential to use effective barrier contraception during treatment with VORANIGO and for at least 3 months after the last dose.
7.1. Special Populations
7.1.1. Pregnancy
There are no data from the use of vorasidenib in pregnant women. Based on findings from animal studies, VORANIGO can cause fetal harm when administered to a pregnant woman. In animal embryo-fetal development studies, oral administration of vorasidenib to pregnant rats or rabbits during the period of organogenesis caused embryo-fetal toxicities including malformations, early and late resorptions, and post-implantation losses at exposures above those attained at the maximum human recommended dose (MRHD) of 40 mg based on the area under the concentration-time curve (AUC) (see 16 Non-clinical toxicology).
Women of childbearing potential should use an effective non-hormonal method of contraception when taking VORANIGO.
VORANIGO is not recommended during pregnancy and in women of childbearing potential not using contraception. Pregnant women, women of childbearing potential or male patients with female partners of childbearing potential should be advised on the potential risk to a fetus.
Pregnancy testing
Pregnancy testing is recommended in women of childbearing potential prior to starting treatment with VORANIGO.
7.1.2. Breastfeeding
No data exist on whether vorasidenib and its metabolites are excreted in human milk. Breast-feeding should be discontinued during treatment with VORANIGO and for at least 2 months after the last dose.
7.1.3. Pediatrics
Pediatrics (>12 years): No patients under the age of 18 were treated with VORANIGO in the pivotal phase 3 study (INDIGO). Use of VORANIGO in pediatric patients 12 years and older is supported by evidence from studies in adults with additional population pharmacokinetic data demonstrating that age had no clinically meaningful effect on the pharmacokinetics of vorasidenib, that the exposure of vorasidenib is mostly similar between adults and pediatric patients age 12 years and older, and that the course of disease is sufficiently similar in adult and pediatric patients to allow extrapolation of data in adults to these pediatric patients. Analysis of the population pharmacokinetic modelling indicated that pediatric female patients in the 40-50 kg weight range may have a higher exposure and a higher risk of adverse drug reactions (see 10.3 Pharmacokinetics, 14.1 Clinical Trials by Indication, and 4.2 Recommended Dose and Dosage Adjustment, Dosage Modifications).
7.1.4. Geriatrics
Geriatrics (>65 years): Of the 167 patients who were randomized and received VORANIGO 40 mg once daily in the INDIGO trial, 1.2% (2 patients) were 65 years or older. No overall differences in safety or effectiveness were observed for patients aged 65 years or older (see 10.3 Pharmacokinetics).
8. Adverse Reactions
8.1. Adverse Reaction Overview
In the INDIGO trial, the most common adverse reactions in Table 4 under VORANIGO reported in ≥1% of treated patients with a ≥2% difference between arms compared with Placebo, including laboratory abnormalities, were ALT increased (36.5%), AST increased (24.6%), fatigue (23.4%), GGT increased (13.2%), and diarrhea (12%).
The most common grade ≥3 adverse reactions were ALT increased (9.6%), AST increased (4.2%) and GGT increased (2.4%).
Serious adverse reactions were reported in 1 of 167 patients (0.6%) who received VORANIGO. The most common serious adverse reaction was ALT increased (0.6%).
Permanent discontinuation of VORANIGO was reported in 5 of 167 patients (3.0%). The most common adverse reaction leading to permanent discontinuation was ALT increased (3%).
Dose interruptions due to an adverse reaction occurred in 31 of 167 patients (18.6%) treated with VORANIGO. The most common adverse reactions requiring dose interruption were ALT increased (14.4%) and AST increased (6%).
Dose reductions of VORANIGO due to an adverse reaction occurred in 10.2% of patients. The most common adverse reaction requiring dose reduction was ALT increased (7.8%).
8.2. Clinical Trial Adverse Reactions
Clinical trials are conducted under very specific conditions. Therefore, the frequencies of adverse reactions observed in the clinical trials may not reflect frequencies observed in clinical practice and should not be compared to frequencies reported in clinical trials of another drug.
Adverse reactions reported in patients treated with VORANIGO in the INDIGO trial (Study AG881-C-004) are listed below by MedDRA system organ class and by frequency are presented in Table 4.
Table 4 − Adverse Reactions Reported in ≥1% of Patients Receiving VORANIGO with a Difference Between Arms of ≥2% Compared with Placebo in the INDIGO Trial (Study AG881-C-004)
| System Organ Classa | VORANIGO N=167 | Placebo N=163 | ||
| Parameter | Any grade n (%) | Grades 3-4 n (%) | Any grade n (%) | Grades 3-4 n (%) |
| Metabolism and nutrition disorders | ||||
| Decreased appetite | 9 (5.4) | 0 | 5 (3.1) | 0 |
| Gastrointestinal disorders | ||||
| Diarrheab | 20 (12.0) | 1 (0.6) | 16 (9.8) | 1 (0.6) |
| Abdominal painc | 13 (7.8) | 0 | 6 (3.7) | 0 |
| Gastroesophageal reflux diseased | 7 (4.2) | 0 | 1 (0.6) | 0 |
| General Disorders | ||||
| Fatiguee | 39 (23.4) | 1 (0.6) | 33 (20.2) | 1 (0.6) |
| Investigations | ||||
| ALT increased | 61 (36.5) | 16 (9.6) | 18 (11) | 0 |
| AST increased | 41 (24.6) | 7 (4.2) | 9 (5.5) | 0 |
| GGT increased | 22 (13.2) | 4 (2.4) | 5 (3.1) | 1 (0.6) |
| Blood alkaline phosphatase increased | 6 (3.6) | 0 | 2 (1.2) | 0 |
a Adverse reactions are listed according to MedDRA version 25.1 system organ class. b Grouped term diarrhea includes diarrhea, feces soft, and frequent bowel movements. c Grouped term abdominal pain includes abdominal pain, abdominal pain upper, and abdominal discomfort. d Grouped term gastroesophageal reflux disease includes gastroesophageal reflux disease, gastritis, and dyspepsia. e Grouped term fatigue includes fatigue and asthenia. | ||||
8.2.1. Clinical Trial Adverse Reactions – Pediatrics
No pediatric safety data were obtained in the clinical trials (see 7.1.3 Pediatrics >12 years).
8.3. Less Common Clinical Trial Adverse Reactions
Not applicable.
8.3.1. Less Common Clinical Trial Adverse Reactions – Pediatrics
No pediatric safety data were obtained in the clinical trials.
8.4. Abnormal Laboratory Findings: Hematologic, Clinical Chemistry, and Other Quantitative Data
Clinical Trial Findings
Table 5 – Selected New or Worsened Laboratory Abnormalities ≥1% Reported in Patients Receiving VORANIGO with a Difference Between Arms of ≥2% Compared with Placebo in the INDIGO Trial (Study AG881-C-004)
VORANIGO N=167 | Placebo N=163 | ||||||||||||
|---|---|---|---|---|---|---|---|---|---|---|---|---|---|
| Parameter | Any grade n (%) | Grades 3 – 4 n (%) | Any grade n (%) | Grades 3 – 4 n (%) | |||||||||
| Alanine aminotransferase (ALT) increased | 99 (59.3) | 16 (9.6) | 41 (25.2) | 0 | |||||||||
| Aspartate aminotransferase (AST) increased | 76 (45.5) | 8 (4.8) | 33 (20.2) | 0 | |||||||||
| Blood alkaline phosphatase increased | 16 (9.6) | 2 (1.2) | 11 (6.7) | 1 (0.6) | |||||||||
| Gamma-glutamyl transferase (GGT) increased | 63 (37.7) | 5 (3.0) | 17 (10.4) | 3 (1.8) | |||||||||
| Platelet count decreased | 20 (12) | 0 | 7 (4.3) | 0 | |||||||||
8.5. Post-Market Adverse Reactions
The following list of adverse reactions have been reported from post-marketing experience with VORANIGO. These reactions are derived from sources including spontaneous reports and compassionate use programmes for which it is not always possible to reliably establish frequency or a causal relationship to exposure of the medicinal product.
Hepatobiliary disorders: blood bilirubin increased, drug-induced liver injury, autoimmune hepatitis, hepatic necrosis, and hepatitis acute (see sections 4 Dosage and administration and 7 Warnings and Precautions).
9. Drug Interactions
9.4. Drug-Drug Interactions
The drugs listed in this table are based on either drug interaction case reports or studies, or potential interactions due to the expected magnitude and seriousness of the interaction (i.e., those identified as contraindicated).
Table 6 – Established or Potential Drug-Drug Interactions
| Proper name | Source of Evidence | Effect | Clinical comment |
| Proper name | Source of Evidence | Effect | Clinical comment |
Moderate and Strong Cytochrome P450 (CYP) 1A2 Inhibitors ciprofloxacin (moderate CYP1A2 inhibitor) fluvoxamine (strong CYP1A2 inhibitor) | CT CT T | Concomitant use of 20 mg VORANIGO with a moderate CYP1A2 inhibitor (500 mg ciprofloxacin twice daily for 14 days) increased vorasidenib plasma Cmax by 1.3-fold and AUC by 2.5-fold. Concomitant use of VORANIGO with strong inhibitors of CYP1A2 (fluvoxamine) is predicted to increase vorasidenib Cmax by 5.7-fold and exposure by 7.2-fold. | Avoid concomitant use of VORANIGO with a moderate and strong CYP1A2 inhibitor. If concomitant use cannot be avoided, monitor for increased adverse reactions and modify the dosage as recommended (see Table 2). |
Moderate CYP1A2 Inducers phenytoin and rifampicin | CT T | Concomitant use of VORANIGO with moderate CYP1A2 inducers and smoking tobacco is predicted to decrease vorasidenib steady-state Cmax and AUC by 30 to 40%, which may decrease the efficacy of VORANIGO. | Avoid concomitant use of VORANIGO with moderate CYP1A2 inducers and smoking tobacco. |
CYP Substrates with Narrow Therapeutic Index alfentanil, carbamazepine, cyclosporine, everolimus, fentanyl, ifosfamide, pimozide, quinidine, sirolimus, tacrolimus, tamoxifen | T | VORANIGO may decrease plasma concentrations and therapeutic effect of medications that are CYP2C19 and CYP3A4 substrates, where minimal concentration changes may lead to reduced therapeutic effect. | Avoid concomitant use of VORANIGO with CYP2C19 and CYP3A4 substrates where minimal concentration changes may lead to reduced efficacy. |
| Hormonal Contraceptives | T | Co-administration of VORANIGO may decrease concentrations of hormonal contraceptives which may lead to contraception failure. | Concomitant use of a barrier method of contraception is recommended during the treatment and for at least 3 months after the last dose. |
Legend: C = Case Study; CT = Clinical Trial; T = Theoretical
Gastric Acid Reducing Agents
In healthy subjects, co-administration of a single dose of 50 mg vorasidenib with 40 mg of omeprazole under fasted conditions, after repeated dosing of omeprazole 40 mg once daily for 3 days, did not have a significant effect on vorasidenib exposure.
CYP Substrates
Based on physiologically-based pharmacokinetic modeling, vorasidenib is predicted to have a strong induction effect on sensitive CYP3A substrates; weak-to-moderate induction effect on sensitive CYP2C19 substrates and weak induction effect on sensitive CYP2B6 substrates.
UGT1A4 Substrate
No clinically significant difference in lamotrigine pharmacokinetics was observed following the administration of lamotrigine with multiple doses of vorasidenib.
P-gp and BCRP substrates
In a model approach, vorasidenib is not predicted to have effect on pharmacokinetics of digoxin (P-gp substrate) and rosuvastatin (BCRP substrate).
In vitro Studies
Effect of vorasidenib on Drug Metabolizing Enzymes
Vorasidenib is an inducer of CYP2B6, CYP2C8, CYP2C9, CYP2C19, CYP3A and UGT1A4.
Effect of vorasidenib on transporter Mediated Drug-Drug Interaction
Vorasidenib is not a substrate of P-gp, BCRP, or OATP1B1 and OATP1B3. Vorasidenib may be an inhibitor of BCRP. Vorasidenib does not inhibit P-gp or SLC transporters. AGI-69460, a metabolite of vorasidenib, may be an inhibitor of OATP1B3.
9.5. Drug-Food Interactions
All clinical studies administered VORANIGO on modified fasting. VORANIGO should be taken after at least 2 hours of fasting, and food intake should be avoided for at least 1 hour after taking VORANIGO since high- and low-fat meals can lead to increased plasma concentrations.
9.6. Drug-Herb Interactions
Interactions with herbal products have not been established.
9.7. Drug-Laboratory Test Interactions
Interactions with laboratory tests have not been established.
10. Clinical Pharmacology
10.1. Mechanism of Action
Vorasidenib is a small molecule inhibitor of IDH1 and IDH2 enzymes. From in vitro and in vivo tumour models expressing IDH1 or IDH2 proteins, vorasidenib inhibited the IDH1 and IDH2 wild type and variants, including IDH1 R132H. Vorasidenib decreased the production of 2-hydroxyglutarate (2-HG) and may restore cellular differentiation.
10.2. Pharmacodynamics
Vorasidenib decreases 2-HG tumour concentrations in patients with IDH1 or IDH2 mutated glioma. Relative to tumours from subjects in the untreated group, the posterior median percentage reduction in tumour 2-HG was 63.5% (95% Credible Interval: 22.2%, 88.4%) to 92.6% (95% Credible Interval: 76.1%, 97.6%) in tumours from patients who received vorasidenib at exposures that were 0.3 to 0.8 times the exposure observed with the approved recommended dosage.
Cardiac electrophysiology
Vorasidenib did not prolong the QT interval to any clinically relevant extent at 4 times the recommended therapeutic dosage.
10.3. Pharmacokinetics
Vorasidenib maximum plasma concentration (Cmax) and area under the curve (AUC) increases in a proportional manner between 10 and 50 mg.
Table 7 − Summary of vorasidenib Pharmacokinetic Parameters in fasted healthy adult population
| Cmax (ng/mL)* | Tmax (hr)* | t½ (hr)* | AUC0-∞ (hr∙ng /mL)* | CL/F (L/hr)* | Vd/F (L)* | |
| Single dose | 75.4 (44%) | 2.0 (0.5, 4.1) | 238 (57%) | 2,860 (56%) | 14.0 (56%) | 3,930 (40%) |
* PK parameters expressed as geometric mean (geometric CV%) except Tmax which is summarized as median (min, max)
Absorption
Vorasidenib steady state mean (CV%) Cmax was 133 ng/mL (73%) and AUC was 1,988 hr∙ng/mL (95%).
Accumulation ratios were approximately 3.83 for Cmax and 4.43 for AUC. Steady-state plasma levels were reached after 14 days of once-daily dosing.
Food effect
The mean Cmax and AUCT increased by 3.1-fold and 1.4-fold, respectively, when vorasidenib was administered with a high-fat meal. Administration of vorasidenib with a low-fat meal resulted in increases in Cmax and AUCT of 2.3- and 1.4-fold, respectively.
Distribution
Vorasidenib steady state mean (CV%) volume of distribution (Vd/F) is 3,930 L (40%).
The mean plasma protein binding of vorasidenib is 97% independent of concentration. The brain tumour-to-plasma concentration ratio is 1.6.
Metabolism
Vorasidenib is primarily metabolized by CYP1A2 with minor contributions from CYP2B6, CYP2C8, CYP2C9, CYP2C19, CYP2D6, and CYP3A4/5. Non-CYP pathways may contribute up to 30% of vorasidenib liver metabolic clearance.
Elimination
Following oral administration of radiolabeled vorasidenib, 85% of the dose was recovered in feces and 4.5% in urine. Most of the administered radioactivity that was recovered in feces was unchanged vorasidenib (55%) while no unchanged vorasidenib was detected in urine.
Special Populations and Conditions
Pediatrics No patients under the age of 18 were treated with VORANIGO in the pivotal phase 3 study (INDIGO). Use of VORANIGO in pediatric patients 12 years and older is supported by evidence from studies in adults with additional population pharmacokinetic data demonstrating that age had no clinically meaningful effect on the pharmacokinetics of vorasidenib, that the exposure of vorasidenib is mostly similar between adults and pediatric patients age 12 years and older, and that the course of disease is sufficiently similar in adult and pediatric patients to allow extrapolation of data in adults to these pediatric patients. Analysis of the population pharmacokinetic modelling indicated that female pediatric patients in the 40-50 kg weight range may have a higher exposure and a higher risk of adverse drug reactions (see 7 Warnings and precautions, 14.1 Clinical Trials by Indication, and 4.2 Recommended Dose and Dosage Adjustment, Dosage Modifications).
The safety and effectiveness of VORANIGO have not been established in pediatric patients less than 12 years of age with Grade 2a astrocytoma or oligodendroglioma who have an IDH1 or IDH2 mutation.
a. WHO 2016, 2021 guidelines
- Geriatrics (> 65 years) Of the 167 patients randomized to receive VORANIGO 40 mg once daily in the INDIGO trial, 1.2% (2 patients) were 65 years or older. No overall differences in safety or effectiveness were observed in patients aged 65 years or older.
- Sex No clinically significant effects on the pharmacokinetics of vorasidenib were observed based on sex. Elevated liver laboratory tests were seen more often in female patients, however the cause for such is unknown. All patients should have their liver laboratory tests monitored as described above.
- Ethnic Origin No clinically significant effects on the pharmacokinetics of vorasidenib were observed based on age (16 to 75 years), race (White, Black or African American, Asian, American Indian/Alaskan Native, Native Hawaiian or Other Pacific Islander, Other), ethnicity (Hispanic and non-Hispanic) or body weight (43.5 to 168 kg).
- Hepatic Insufficiency No clinically significant effects on the pharmacokinetics of vorasidenib were observed based on mild or moderate hepatic impairment (Child-Pugh Class A or B). The pharmacokinetics of vorasidenib have not been studied in patients with severe hepatic impairment (Child-Pugh Class C) (see 4.2 Recommended Dose and Dosage Adjustment and 7 Warnings and precautions, Hepatic/Biliary/Pancreatic).
- Renal Insufficiency No clinically significant effects on the pharmacokinetics of vorasidenib were observed based on mild or moderate renal impairment (CLcr >40 mL/min). The pharmacokinetics of vorasidenib have not been studied in patients with CLcr ≤40 mL/min or renal impairment requiring dialysis (see 7 Warnings and precautions).
- Storage, Stability, and Disposal
Store at room temperature (15°C to 30°C).
Once opened, VORANIGO should be used within 60 days.
Keep out of reach and sight of children.
Part 2: Scientific Information
13. Pharmaceutical Information
Drug Substance
Proper/common name: vorasidenib
Chemical name: 6-(6-chloropyridin-2-yl)-N2,N4-bis[(2R)-1,1,1-trifluoropropan-2-yl]-1,3,5-triazine-2,4-diamine, 2-hydroxypropane-1,2,3-tricarboxylic acid, hydrate (2:1:1)
Molecular formula and molecular mass:
The molecular formula is C14H13ClF6N6 · ½ C6H8O7· ½ H2O and the molecular weight is 519.8 g/mol.
Structural formula:
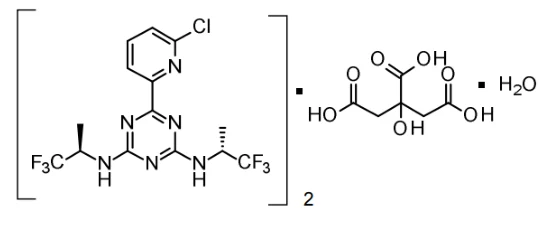
Physicochemical properties: vorasidenib (as vorasidenib hemicitric acid, hemihydrate) is a white to off-white solid and is practically insoluble in aqueous solutions between pH 1.2 to 6.8.
14. Clinical Trials
14.1. Clinical Trials by Indication
Grade 2 IDH 1/2 Mutant Glioma
INDIGO trial (AG881-C-004)
Table 8 − Summary of patient demographics for INDIGO clinical trial in Grade 2 IDH1/2 mutant glioma
| Study # | Study design | Dosage, route of administration and duration | Study subjects (n) | Median age (Min, Max) | Sex (%) |
| AG881-C-004 | Phase 3, randomized (1:1), multicenter, double-blind, placebo-controlled | 40 mg orally once daily or matched placebo until radiographic disease progression or unacceptable toxicity | VORANIGO n=168 placebo n=163 | 40.5 (21-71) 39 (16-65) | M 60.1 / F 39.9 M 52.8 / F 47.2 |
The efficacy of VORANIGO was evaluated in the INDIGO trial (Study AG881-C-004), a phase 3, randomized (1:1), multicenter, double-blind, placebo-controlled study of 331 adults and pediatric patients ≥12 years old weighing ≥40 kg. Eligible patients were required to have Grade 2 astrocytoma or oligodendroglioma with an IDH1 R132 mutation or IDH2 R172 mutation and prior surgery (gross total resection, subtotal resection or biopsy) for glioma. Patients with non-enhancing tumours or minimal tumour enhancement (includes tumours with no enhancement or minimal, non-nodular, and non-measurable enhancement that has not changed between the 2 most recent scans), including non-nodular or non-measurable lesions, were permitted to enroll. The INDIGO trial excluded patients who received prior anti-cancer treatment, including chemotherapy or radiation therapy. IDH1 or IDH2 mutation status was prospectively determined using the Oncomine Dx Target Test.
Patients were randomized to receive either VORANIGO 40 mg orally once daily or matched placebo until radiographic disease progression or unacceptable toxicity. Randomization was stratified by local 1p19q status (co-deleted or not co-deleted) and baseline tumour size (diameter ≥2 cm or <2 cm). Patients who were randomized to placebo were allowed to cross over to receive VORANIGO after centrally confirmed radiographic disease progression.
Patient demographics and disease characteristics were balanced between the treatment arms. Among the 168 patients randomized to VORANIGO, the median age was 41 years (range: 21 to 71 years), with 98.8% aged 18-64 years. A single pediatric patient aged 16 years was randomized to placebo, and no patient under the age of 18 was randomized to VORANIGO. A majority of patients were male (60.1%), 74.4% were White, 3.0% Asian, 1.2% Black, 1.2% other, 19.6% not reported and 53.6% had a Karnofsky Performance Status (KPS) score of 100. Most patients had 1 prior surgery for glioma (75%) and 25% had ≥2 prior surgeries (50.6% gross total, 48.2% sub-total, 14.3% biopsy). Across both arms, 95% of patients had an R132 mutation and 5% had an R172 mutation.
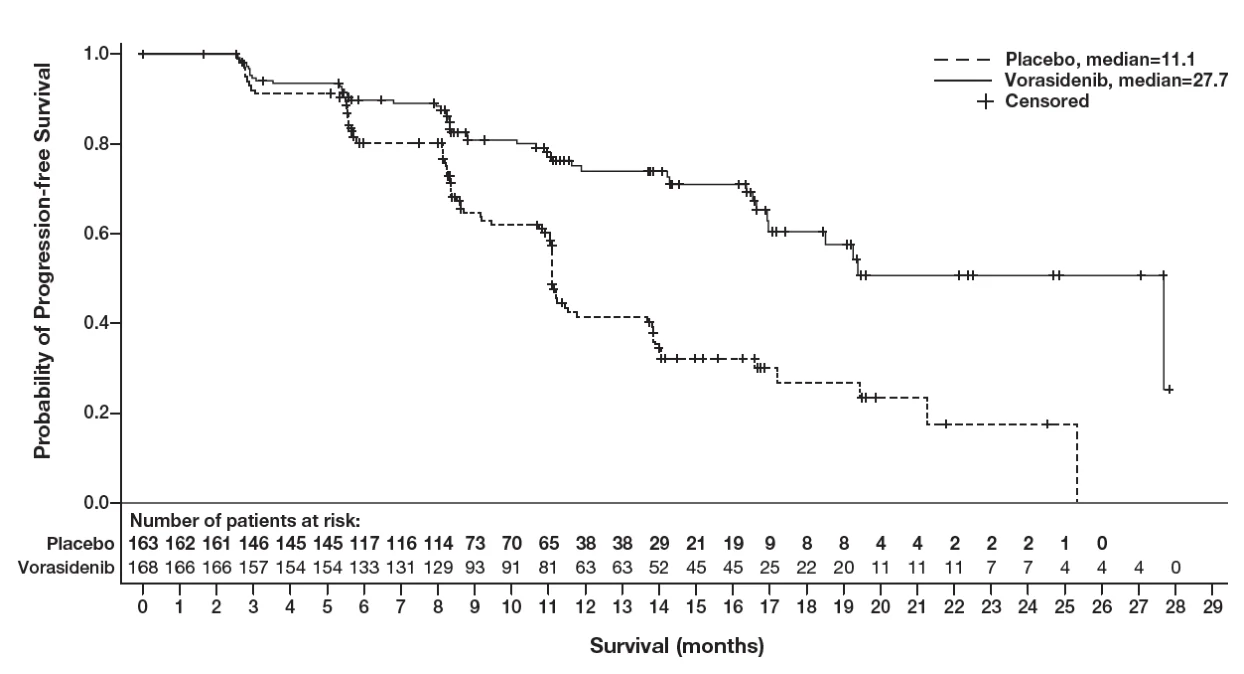
The primary efficacy outcome measure was radiographic progression-free survival (PFS) as evaluated by a blinded independent review committee (BIRC) according to modified Response Assessment in Neuro-Oncology for Low Grade Glioma (RANO-LGG) criteria. Time to next intervention (TTNI), the time from randomization to the initiation of first subsequent anticancer therapy or death due to any cause, was the key secondary outcome measure.
Efficacy results for PFS and TTNI are summarized in Table 9 and Figure 1.
| Table 9 − Efficacy Results for INDIGO Trial (Study AG881-C-004) | ||||||||
|---|---|---|---|---|---|---|---|---|
| Table 9 − Efficacy Results for INDIGO Trial (Study AG881-C-004) | ||||||||
| Efficacy parameter | VORANIGO 40 mg daily (n=168)a | Placebo (n=163) | ||||||
| Efficacy parameter | VORANIGO 40 mg daily (n=168)a | Placebo (n=163) | ||||||
| Progression-free survival (PFS) | ||||||||
Number of events, n (%) Progressive disease Death | 47 (28.0) 0 | 88 (54.0) 0 | ||||||
| Median PFS, months (95% CI)b | 27.7 (17.0, NE) | 11.1 (11.0, 13.7) | ||||||
| Hazard ratio (95% CI)c | 0.39 (0.27, 0.56) | |||||||
| p-valued | 0.000000067 | |||||||
| Time to next intervention (TTNI) | ||||||||
Number of events, n (%) First subsequent therapy Crossover to VORANIGO | 19 (11.3) 0 | 6 (3.7) 52 (31.9) | ||||||
| Median TTNI, months (95% CI)b | NE (NE, NE) | 17.8 (15.0, NE) | ||||||
| Hazard ratio (95% CI)c | 0.26 (0.15, 0.43) | |||||||
| p-valuee | 0.000000019 | |||||||
Abbreviations: CI = Confidence interval; NE = Not estimable; PFS = Progression-free survival; TTNI = Time to next intervention a The efficacy analyses were based on all patients who were randomized. b The 95% confidence interval for the median was calculated using the Brookmeyer and Crowley method. c Estimated with Cox proportional hazard model adjusted by the following stratification factors: 1p19q status and baseline tumour size. d Based on one-sided stratified log-rank test compared to the pre-specified α of 0.000359 (one-sided). e Based on one-sided stratified log-rank test compared to the pre-specified α of 0.00000048 (one-sided). | ||||||||
Figure 1: Kaplan-Meier Curve for Progression-Free Survival per BIRC Review in INDIGO Trial
15. Microbiology
No microbiological information is required for this drug product.
16. Non-Clinical Toxicology
General toxicology
In repeat-dose studies, vorasidenib was administered orally in Sprague Dawley rats (both sexes) for 13 weeks at daily doses of 5, 15 and 50 mg/kg (up to 176-fold the MRHD of 40 mg based on AUC), and in cynomolgus monkeys (both sexes) for 13 weeks at daily doses of 2, 6 and 20 mg/kg (up to 73-fold the MRHD of 40 mg based on AUC).
The following adverse effects in rats and monkeys were considered related to vorasidenib. Hepatocellular hypertrophy, increase in liver weight and changes in liver enzymes (AST, ALT, GGT, sorbitol dehydrogenase (SDH) and ALP) were observed in both sexes of rats (at least 5 mg/kg/day; at least 29-fold the MRHD of 40 mg based on AUC) and of monkeys (at least 6 mg/kg/day; at least 9-fold the MRHD of 40 mg based on AUC). Effects on neuromuscular system such as tremor, ataxia, head tilt, decrease in muscle tone, effects on skin such as desquamation, redness and hyperplasia, and effects on the kidneys such as mixed inflammatory cell infiltrates, tubular degeneration and decrease in kidney weight were observed in the high dose groups of both species. Reversible changes in erythrocyte and reticulocyte counts, red blood cell distribution, hemoglobin, platelets and fibrinogen levels were observed in both sexes of rats (at least 15 mg/kg/day; at least 77-fold the MRHD of 40 mg based on AUC) and in monkeys (at least 6 mg/kg/day; at least 9-fold the MHRD of 40 mg based on AUC).
Other effects such as decrease in body weight and food consumption as well as effects on gastrointestinal tract were mainly observed in high dose groups of rats.
After a recovery phase of four weeks, the effects in the liver and the changes in the liver enzymes either persisted or partially resolved in both rats and monkeys, depending on the dose level. Partial recovery was noted for skin hyperplasia in rats.
The 28-day administration of vorasidenib at or more than 3 mg/kg/day in male and female rats (at least 8-fold the MRHD of 40 mg based on AUC) caused a reversible and minimal neutrophil infiltration of the epithelial lining of the middle ear and Eustachian tube (otitis media) in both sexes.
Genotoxicity
Vorasidenib was not genotoxic at maximum tested limits. Vorasidenib was not mutagenic in an in vitro bacterial reverse mutation assay in five bacteria strains. Vorasidenib was not clastogenic or aneugenic in an in vitro chromosomal aberration assay in cultured human peripheral blood lymphocytes, nor in an in vivo micronucleus assay in bone marrow of rats treated with oral doses up to 2000 mg/kg.
Carcinogenicity
No long-term animal studies have been performed to evaluate the carcinogenic potential of vorasidenib.
Reproductive and developmental toxicology
Fertility
No fertility animal studies have been performed to evaluate whether vorasidenib affects fertility in males or females. In a 13-week repeat-dose study, male and female rats were administered vorasidenib orally at daily doses of 5, 15 and 50 mg/kg (exposure up to 176-fold the MRHD of 40 mg based on AUC). Adverse effects in female and male reproductive organs were observed from a dose of 5 mg/kg/day (approximately 29-fold the MRHD based on AUC). Adverse effects in females included atrophy of the ovaries, hyperplasia in the epithelia of uterus, cervix and vagina, uterine squamous metaplasia, decreased numbers of corpora lutea and estrous cycle variations. Adverse effects in males included degeneration of seminiferous tubules with germ loss and/or exfoliation into tubular lumen, cellular debris in the epididymis, atrophy of the testis, the epididymis, the prostate (with mixed cell inflammation) and seminal vesicles. After a recovery phase of 4 weeks, partial recovery was observed in both sexes at doses of at least 15 mg/kg/day (at least 77-fold the MRHD of 40 mg based on AUC).
Embryo-fetal Development
Embryo-fetal development was evaluated in female rats administered vorasidenib orally during organogenesis (gestation days 6 to 17) at daily doses of 10, 25 and 75 mg/kg (exposure up to 118-fold the MRHD of 40 mg based on AUC). At daily dose of 75 mg/kg (118-fold the MRHD based on AUC), increases in early and late resorptions and post-implantation losses, higher incidences of visceral abnormalities were observed, and fetal body weights were 20% lower than concurrent controls. Higher incidences of skeletal abnormalities were observed at all dose levels (at least 31-fold the MRHD based on AUC).
Embryo-fetal development was evaluated in pregnant rabbits administered vorasidenib orally during organogenesis (gestation days 6 to 19) at daily doses of 2, 6 and 18 mg/kg resulting in clinically relevant exposures at the daily MRHD of 40 mg based on AUC. At daily dose of 18 mg/kg (exposure of 12-fold the MRHD of 40 mg based on AUC), increases in embryo-fetal resorptions and post-implantation losses were observed, and fetal body weights were 8% lower than concurrent controls. Higher incidences of delayed ossification and other skeletal variations were observed at daily doses of at least 6 mg/kg/day (exposure of at least 5-fold the MRHD based on AUC).
In both species, dose-dependent decreases in maternal food intake and body weight gain were observed during gestation.