


Product Monograph - Yasmin 21
Recent Major Label Changes
Not applicable
Table of Contents
Certain sections or subsections that are not applicable at the time of the preparation of the most recent authorized product monograph are not listed.
Table of Contents .............................................................................................................. 2
Part 1: Health Professional Information ............................................................................. 4
1 Indications ................................................................................................................... 4
1.1 Pediatrics .......................................................................................................................... 4
1.2 Geriatrics .......................................................................................................................... 4
2 Contraindications ......................................................................................................... 4
3 Serious Warnings and Precautions Box ......................................................................... 5
4 Dosage and Administration .......................................................................................... 5
4.2 Recommended Dose and Dosage Adjustment ................................................................ 5
4.4 Administration.................................................................................................................. 5
4.5 Missed Dose ..................................................................................................................... 7
5 Overdose ...................................................................................................................... 8
6 Dosage Forms, Strengths, Composition, and Packaging ................................................. 8
7 Warnings and Precautions ............................................................................................ 9
General ................................................................................................................................. 9
Carcinogenesis and Genotoxicity ......................................................................................... 10
Cardiovascular ...................................................................................................................... 10
Driving and Operating Machinery ........................................................................................ 11
Endocrine and Metabolism .................................................................................................. 11
Gastrointestinal .................................................................................................................... 11
Genitourinary ....................................................................................................................... 11
Hematologic ......................................................................................................................... 11
Hepatic/Biliary/Pancreatic ................................................................................................... 13
Immune ................................................................................................................................ 14
Monitoring and Laboratory Tests ........................................................................................ 14
Neurologic ............................................................................................................................ 14
Ophthalmologic .................................................................................................................... 15
Perioperative Considerations ............................................................................................... 15
Psychiatric ............................................................................................................................ 15
Renal ................................................................................................................................... 15
Reproductive Health ............................................................................................................ 15
Skin ....................................................................................................................................... 16
7.1 Special Populations ........................................................................................................ 16
7.1.1 Pregnancy ................................................................................................................. 16
7.1.2 Breastfeeding ............................................................................................................ 16
7.1.3 Pediatrics .................................................................................................................. 16
7.1.4 Geriatrics ................................................................................................................... 16
8 Adverse Reactions ...................................................................................................... 16
8.1 Adverse Reaction Overview ........................................................................................... 16
8.2 Clinical Trial Adverse Reactions ..................................................................................... 19
8.3 Less Common Clinical Trial Adverse Reactions .............................................................. 19
8.5 Post-Market Adverse Reactions ..................................................................................... 19
9 Drug Interactions ........................................................................................................ 20
9.2 Drug Interactions Overview ........................................................................................... 20
9.3 Drug-Behaviour Interactions .......................................................................................... 21
9.4 Drug-Drug Interactions .................................................................................................. 21
9.5 Drug-Food Interactions .................................................................................................. 25
9.6 Drug-Herb Interactions .................................................................................................. 25
9.7 Drug-Laboratory Test Interactions ................................................................................. 25
10 Clinical Pharmacology ............................................................................................... 26
10.1 Mechanism of Action ................................................................................................... 26
10.2 Pharmacodynamics ...................................................................................................... 26
10.3 Pharmacokinetics ......................................................................................................... 27
11 Storage, Stability, and Disposal ................................................................................. 30
Part 2: Scientific Information ........................................................................................... 31
13 Pharmaceutical Information ..................................................................................... 31
14 Clinical Trials ............................................................................................................ 33
14.1 Clinical Trial by Indication ............................................................................................ 33
16 Non-Clinical Toxicology ............................................................................................. 34
Patient Medication Information ...................................................................................... 38
Part 1: Health Professional Information
1 Indications
YASMIN (drospirenone and ethinyl estradiol tablet) is indicated for:
- Conception Control
- Treatment of moderate acne vulgaris in women ≥16 years of age who have no known contraindications to oral contraceptive therapy, desire contraception, and have achieved menarche
1.1 Pediatrics
Pediatrics (˂16 years of age): The safety and efficacy of YASMIN has not been established in women under the age of 16 years. Use of this product before menarche is not indicated (see 7.1.3 Pediatrics).
1.2 Geriatrics
Geriatrics: YASMIN is not indicated for use in postmenopausal women. No data are available to Health Canada; therefore, Health Canada has not authorized an indication for geriatric use.
2 Contraindications
YASMIN should not be used in women with:
- a history of or actual thrombophlebitis or thromboembolic disorders
- a history of or actual cerebrovascular disorders
- a history of or actual myocardial infarction or coronary artery disease
- valvular heart disease with complications
- history of or actual prodromi of a thrombosis (e.g., transient ischemic attack, angina pectoris)
presence of severe or multiple risk factor(s) for arterial or venous thrombosis:
- severe hypertension (persistent values of ≥160/100 mmHg)
- hereditary or acquired predisposition for venous or arterial thrombosis, such as Factor V Leiden mutation and activated protein C (APC-) resistance, antithrombin-III-deficiency, protein C deficiency, protein S deficiency, hyperhomocysteinemia and antiphospholipid antibodies (anticardiolipin antibodies, lupus anticoagulant)
- severe dyslipoproteinemia
- smoking, if over age 35
- diabetes mellitus with vascular involvement
- major surgery associated with an increased risk of postoperative thromboembolism
- prolonged immobilization
- use with the Hepatitis C virus combination drug regimen ombitasvir, paritaprevir, ritonavir, with or without dasabuvir (see 7 Hepatic/Biliary/Pancreatic)
- active liver disease or history of or actual benign or malignant liver tumors
- known or suspected carcinoma of the breast
- carcinoma of the endometrium or other known or suspected estrogen-dependent neoplasia
- undiagnosed abnormal vaginal bleeding
- steroid-dependent jaundice, cholestatic jaundice, history of jaundice in pregnancy
- any ocular lesion arising from ophthalmic vascular disease, such as partial or complete loss of vision or defect in visual fields
- known or suspected pregnancy
- current or history of migraine with focal aura
- history of or actual pancreatitis if associated with severe hypertriglyceridemia
- renal insufficiency
- hepatic dysfunction
- adrenal insufficiency
- hypersensitivity to this drug or to any ingredient in the formulation or component of the container. For a complete listing, see 6 Dosage Forms, Strengths, Composition, and Packaging.
3 Serious Warnings and Precautions Box
|
|---|
4 Dosage and Administration
4.2 Recommended Dose and Dosage Adjustment
Take one tablet by mouth at the same time every day. The failure rate may increase when pills are missed or taken incorrectly.
It is recommended that YASMIN tablets should be taken every day at about the same time regardless of mealtimes and as directed on the package.
4.4 Administration
Conception Control
Tablets must be taken in the order directed on the package every day at about the same time. The patient may begin using YASMIN on Day 1 of her menstrual cycle (i.e., the first day of menstrual flow), on Day 5, or on the first Sunday after her period begins. If the patient’s period begins on Sunday, she should start that same day. If YASMIN tablets are taken later than Day 1 when first starting medication, an additional (barrier) method of birth control is recommended for the first seven days of use.
YASMIN 21 (21-Day Regimen)
One hormone-containing yellow tablet is to be taken daily for 21 consecutive days. Tablets are then discontinued for 7 consecutive days. Withdrawal bleeding usually occurs within 2 to 3 days following discontinuation.
The patient begins each subsequent course of YASMIN 21 tablets on the same day of the week that she began her first course. She begins taking her next course on the 8th day after discontinuation, regardless of whether or not withdrawal bleeding is still in progress.
YASMIN 28 (28-Day Regimen)
One hormone-containing yellow tablet is to be taken daily for 21 consecutive days, followed by one hormone-free white tablet daily for 7 consecutive days. Withdrawal bleeding usually occurs within 2 to 3 days following the last hormone-containing yellow tablet (i.e., while the patient is taking the hormone-free white tablets).
The patient begins each subsequent course of YASMIN 28 tablets on the same day of the week that she began her first course. She begins taking her next course immediately after completion of the last course, regardless of whether or not withdrawal bleeding is still in progress. There is no need for the patient to count days between cycles because there are no “off-tablet days.”
Acne
The timing of initiation of YASMIN 21 and YASMIN 28 treatment for acne should follow the instructions for use of YASMIN 21 and YASMIN 28 for contraception (see 4.2 Conception Control).
Special Notes on Administration
Switching from another combined hormonal contraceptive (combined oral contraceptive (COC), vaginal ring, or transdermal patch)
The patient should start YASMIN on the day she would normally start her next pack of combined oral contraceptive. In case a vaginal ring or transdermal patch has been used, the woman should start using YASMIN preferably on the day of removal, but at the latest when the next application would have been due.
Switching from a progestogen-only method (mini-pill, injection) or from a Progestogen-releasing Intrauterine System (IUS)
The patient may switch from the mini-pill to YASMIN on any day of her cycle. Patients using a progestogen injection should start YASMIN on the day the next injection is due. Patients using an IUS should start YASMIN on the day the IUS is removed. In all cases, the patient should be advised to use an additional (barrier) method for the first 7 days of YASMIN use.
Following first trimester abortion
The patient may start using YASMIN immediately. When doing so, she need not take additional contraceptive measures.
Following delivery or second trimester abortion
Patients should be advised to start YASMIN on Day 21 to 28 after delivery or second trimester abortion, after consulting with their physician. When starting later, the patient should be advised to use an additional (barrier) method for the first seven days of YASMIN use. However, if intercourse has already occurred, pregnancy should be excluded before the actual start of use or the woman should be advised to wait for her next menstrual period prior to starting YASMIN. When the tablets are administered in the postpartum period, the increased risk of thromboembolic disease associated with the postpartum period must be considered. (see 7.1.2 Breastfeeding)
Withdrawal / Breakthrough bleeding
Withdrawal bleeding usually occurs within 3 days following the last hormone-containing yellow tablet. If spotting or breakthrough bleeding occurs while taking YASMIN, the patient should be instructed to continue taking YASMIN as instructed and by the regimen described above. She should be instructed that this type of bleeding is usually transient and without significance; however, if the bleeding is persistent or prolonged, the patient should be advised to consult her physician.
Although the occurrence of pregnancy is unlikely if YASMIN is taken according to directions, if withdrawal bleeding does not occur, the possibility of pregnancy must be considered. If the patient has not adhered to the prescribed dosing schedule (missed one or more hormone-containing tablets or started taking them on a day later than she should have), the probability of pregnancy should be considered at the time of the first missed period and appropriate diagnostic measures taken before the medication is resumed. If the patient has adhered to the prescribed regimen and misses two consecutive periods, pregnancy should be ruled out before continuing the contraceptive regimen.
Advice in case of vomiting
If vomiting occurs within 3 to 4 hours after a tablet is taken, absorption may not be complete. In such an event, the advice concerning management of missed tablets is applicable.
4.5 Missed Dose
The patient should be instructed to use the following chart if she misses one or more of her birth control pills. She should be told to match the number of tablets missed with the appropriate starting time for her dosing regimen. The risk of pregnancy increases with each hormone-containing yellow tablet missed.
Table 1 – Management of Missed Hormone-Containing Yellow Tablets
| Sunday Start | Other Than Sunday Start |
|---|---|
| Sunday Start | Other Than Sunday Start |
| Miss One Yellow Tablet At Any Time | |
| Take the missed pill as soon as you remember, and take the next tablet at the usual time. This means that you might take two tablets in one day. | |
| Miss Two Yellow Tablets in a Row | |
First Two Weeks:
| |
Third Week
If you miss two periods in a row, call your healthcare professional or clinic. | Third Week
If you miss two periods in a row, call your healthcare professional or clinic. |
| Miss Three or More Yellow Tablets in a Row | |
Anytime in the cycle
If you miss two periods in a row, call your healthcare professional or clinic. | Anytime in the cycle
If you miss two periods in a row, call your healthcare professional or clinic. |
Patients taking YASMIN 28: If the patient forgets any of the seven hormone-free white tablets in Week 4, she should be advised to safely dispose of the tablets she missed, and then to keep taking one tablet each day until the pack is empty. A back-up method of birth control is not required.
5 Overdose
There have been no reports of overdose with YASMIN. Overdosage may cause nausea and vomiting, and withdrawal bleeding may occur in females. Withdrawal bleeding may even occur in girls before their menarche if they have accidentally taken the medicinal product. There are no antidotes and further treatment should be symptomatic, based on the knowledge of the pharmacological action of the constituents. Drospirenone is a spironolactone analogue which has antimineralocorticoid properties. Serum concentration of potassium and sodium and evidence of metabolic acidosis should be monitored in cases of overdose. Liver function tests should be conducted, particularly transaminase levels, 2 to 3 weeks after consumption.
| For the most recent information in the management of a suspected drug overdose, contact your regional poison control centre or Health Canada’s toll-free number, 1-844 POISON-X (1-844-764-7669). |
6 Dosage Forms, Strengths, Composition, and Packaging
Table 2 – Dosage Forms, Strengths, and Composition
YASMIN tablets are available in a 21-day regimen (YASMIN 21) and a 28-day regimen (YASMIN 28) in blister packs.
| Route of Administration | Dosage Form / Strength/Composition | Non-Medicinal Ingredients | ||||
|---|---|---|---|---|---|---|
| Hormone-containing yellow tablet | ||||||
| Oral | Tablet / 3 mg drospirenone and 0.03 mg ethinyl estradiol | corn starch, hydroxypropylmethyl cellulose, lactose monohydrate, magnesium stearate, modified starch, polyethylene glycol, povidone, talc, titanium dioxide and yellow ferric oxide | ||||
| Hormone-free white tablet | ||||||
| No active ingredient | hydroxypropylmethyl cellulose, lactose monohydrate, magnesium stearate, microcrystalline cellulose, talc and titanium dioxide | |||||
Each blister pack consists of 21 hormone-containing yellow, film-coated, round tablets. Each tablet contains 3 mg drospirenone and 0.03 mg ethinyl estradiol. In the 28-day regimen package, there are, in addition, 7 hormone-free white tablets containing inactive ingredients.
7 Warnings and Precautions
Please see 3 Serious Warnings and Precautions Box.
General
Discontinue Medication at the Earliest Manifestation of:
- A. Thromboembolic and cardiovascular disorders such as thrombophlebitis, pulmonary embolism, cerebrovascular disorders, myocardial ischemia, mesenteric thrombosis, and retinal thrombosis.
- B. Conditions that predispose to venous stasis and to vascular thrombosis (e.g., immobilization after accidents or confinement to bed during long-term illness). Other nonhormonal methods of contraception should be used until regular activities are resumed. For use of oral contraceptives when surgery is contemplated, see 7 Perioperative Considerations.
- C. Visual defects - partial or complete
- D. Papilledema, or ophthalmic vascular lesions
- E. Severe headache of unknown etiology or worsening of preexisting migraine headache
- F. Increase in epileptic seizures
The following information is provided from studies of combination oral contraceptives (COCs).
The use of combination hormonal contraceptives is associated with increased risks of several serious conditions including myocardial infarction, thromboembolism, stroke, hepatic neoplasia, and gallbladder disease, although the risk of serious morbidity and mortality is small in healthy women without underlying risk factors. The risk of morbidity and mortality increases significantly if associated with the presence of other risk factors such as hypertension, hyperlipidemias, obesity, and diabetes. Other medical conditions which have been associated with adverse circulatory events include systemic lupus erythematosus, hemolytic uremic syndrome, chronic inflammatory bowel disease (Crohn’s disease or ulcerative colitis), sickle cell disease, valvular heart disease and atrial fibrillation.
The following conditions have been reported to occur or deteriorate with both pregnancy and COC use, although a direct association with COCs has not been firmly established: porphyria, systemic lupus erythematosus, hemolytic uremic syndrome, Sydenham’s chorea, herpes gestationis, and otosclerosis-related hearing loss.
The information contained in this section is principally from studies carried out in women who used combination oral contraceptives with higher formulations of estrogens and progestogens than those in common use today. The effect of long-term use of combination hormonal contraceptives with lower doses of both estrogen and progestogen administered orally remains to be determined.
YASMIN contains 3 mg of the progestogen drospirenone (DRSP) that has antimineralocorticoid activity, including the potential for hyperkalemia in high-risk patients, comparable to a 25 mg dose of spironolactone. YASMIN should not be used in patients with conditions that predispose to hyperkalemia (i.e., renal insufficiency, hepatic dysfunction, and adrenal insufficiency). Women receiving daily, long-term treatment for chronic conditions or diseases with medications that may increase serum potassium should have their serum potassium level checked during the first treatment cycle. Drugs that may increase serum potassium include ACE inhibitors, angiotensin-II receptor antagonists, potassium-sparing diuretics, heparin, aldosterone antagonists, and NSAIDs.
Carcinogenesis and Genotoxicity
Malignancies may be life-threatening or may have a fatal outcome.
Breast Cancer
The frequency of diagnosis of breast cancer is very slightly increased among OC users. As breast cancer is rare in women under 40 years of age, the excess number is small in relationship to the overall risk of breast cancer. Causation with COC use is unknown.
Increasing age and a strong family history are the most significant risk factors for the development of breast cancer. Other established risk factors include obesity, nulliparity, and late age for first full-term pregnancy. The identified groups of women that may be at increased risk of developing breast cancer before menopause are long-term users of oral contraceptives (more than eight years) and starters at early age. In a few women, the use of oral contraceptives may accelerate the growth of an existing but undiagnosed breast cancer. Since any potential increased risk related to oral contraceptive use is small, there is no reason to change prescribing habits at present.
Women receiving oral contraceptives should be instructed in self-examination of their breasts. Their physicians should be notified whenever any masses are detected. A yearly clinical breast examination is also recommended, because, if a breast cancer should develop, drugs that contain estrogen may cause a rapid progression.
Cervical Cancer
The most important risk factor for cervical cancer is persistent human papillomavirus infection (HPV). Some epidemiological studies have indicated that long-term use of COCs may further contribute to this increased risk but there continues to be controversy about the extent to which this finding is attributable to confounding effects, e.g., cervical screening and sexual behaviour including use of barrier contraceptives.
Hepatocellular Carcinoma
Hepatocellular carcinoma may be associated with oral contraceptives. The risk appears to increase with duration of hormonal contraceptive use. However, the attributable risk (the excess incidence) of liver cancers in oral contraceptive users is extremely small. A liver tumor should be considered in the differential diagnosis when severe upper abdominal pain, liver enlargement, or signs of intra-abdominal hemorrhage occur in women taking COCs.
See 16 Non-Clinical Toxicology for discussion of animal data.
Cardiovascular
Predisposing Factors for Coronary Artery Disease
Cigarette smoking increases the risk of serious cardiovascular side effects and mortality. Birth control pills increase this risk, particularly in women over 35 years of age, and with the number of cigarettes smoked. Convincing data are available to support an upper age limit of 35 years for oral contraceptive use by women who smoke. For this reason, combination oral contraceptives, including YASMIN, should not be used by women who are over 35 years of age and smoke.
Other women who are independently at high risk for cardiovascular disease include those with diabetes, hypertension, abnormal lipid profile, or a family history of these. Whether oral contraceptives accentuate this risk is unclear.
In low-risk, nonsmoking women of any age, the benefits of oral contraceptive use outweigh the possible cardiovascular risks associated with low-dose formulations. Consequently, oral contraceptives may be prescribed for these women up to the age of menopause.
Hypertension
Patients with essential hypertension, whose blood pressure is well-controlled, may be given hormonal contraceptives, but only under close supervision. If a significant elevation of blood pressure in previously normotensive or hypertensive subjects occurs at any time during the administration of the drug, cessation of medication is necessary. An increase in blood pressure has been reported in women taking COCs, and this increase is more likely in older women and with extended duration of use.
Driving and Operating Machinery
No studies on the effects of YASMIN on the ability to drive or use machines have been performed.
Endocrine and Metabolism
Diabetes
Current low-dose oral contraceptives exert minimal impact on glucose metabolism. Diabetic patients, or those with a family history of diabetes, should be observed closely to detect any worsening of carbohydrate metabolism. Patients predisposed to diabetes who can be kept under close supervision may be given oral contraceptives. Young diabetic patients whose disease is of recent origin, well-controlled, and not associated with hypertension or other signs of vascular disease such as ocular fundal changes should be monitored more frequently while using oral contraceptives.
Lipid and Other Metabolic Effects
A small proportion of women will have adverse lipid changes while on oral contraceptives. Alternative contraception should be used in women with uncontrolled dyslipidemia (see also 2 Contraindications). Elevations of plasma triglycerides may lead to pancreatitis and other complications.
Gastrointestinal
Published epidemiological studies indicate a possible association of COC use and the development of Crohn’s disease and ulcerative colitis, although this has not been firmly established.
Genitourinary
Vaginal Bleeding
Persistent irregular vaginal bleeding requires assessment to exclude underlying pathology.
Fibroids
Patients with fibroids (leiomyomata) should be carefully observed. Sudden enlargement, pain, or tenderness requires discontinuation of the use of oral contraceptives.
Hematologic
Epidemiological studies have suggested an association between the use of COCs and an increased risk of arterial and venous thrombotic and thromboembolic diseases such as myocardial infarction, deep venous thrombosis, pulmonary embolism, and of cerebrovascular accidents. These events occur rarely.
The use of any combined oral contraceptive carries an increased risk of venous thromboembolism (VTE) compared with no use. The excess risk of VTE is highest during the first year a woman ever uses a combined oral contraceptive or restarts (following a 4-week or greater pill-free interval) the same or a different COC. Data from a large, prospective 3-armed cohort study suggest that this increased risk is mainly present during the first 3 months. VTE is life-threatening and is fatal in 1% to 2% of cases.
A large, prospective 3-armed cohort study has shown that the frequency of VTE diagnosis ranges from about 8 to 10 per 10,000 woman-years in users of oral contraceptives with low estrogen content (<50 µg ethinyl estradiol). The most recent data suggest that the frequency of VTE diagnosis is approximately 4.4 per 10,000 woman-years in nonpregnant, non-COC users and ranges from 20 to 30 per 10,000 woman-years in pregnant women or postpartum.
Overall the risk for VTE in users of oral contraceptives with low estrogen content (<50 µg ethinyl estradiol) is two- to three-fold higher than for nonusers of COCs who are not pregnant and remains lower than the risk associated with pregnancy and delivery.
Several epidemiological studies have examined the risk of VTE with drospirenone-containing COCs versus other COCs. Two prospective cohort studies showed that the risk of VTE with drospirenone-containing COCs is comparable to that of other COCs, including levonorgestrel-containing COCs. One case-control and three retrospective cohort studies suggested that the risk of VTE with drospirenone-containing COCs is higher compared to users of levonorgestrel-containing COCs. Two additional nested case-control studies have reported a two-fold and three-fold increased risk of idiopathic VTE in users of drospirenone-containing COCs as compared with levonorgestrel-containing COCs. These retrospective studies suggest a potential 1.5-3 times risk of VTE in users of drospirenone-containing COCs. Epidemiological studies have inherent methodological issues making the interpretation of their results complex. However, prescribers should consider the benefits and risks for specific patients with respect to VTE risk given the current retrospective epidemiological studies suggesting a higher risk of VTE with drospirenone-containing COCs compared to levonorgestrel-containing COCs.
VTE, manifesting as deep venous thrombosis (DVT) and/or pulmonary embolism (PE), may occur during the use of all COCs.
Extremely rarely, thrombosis has been reported to occur in other blood vessels (e.g., hepatic, mesenteric, renal, cerebral, or retinal veins and arteries) in COC users.
Symptoms of DVT can include: unilateral swelling of the leg or along a vein in the leg; pain or tenderness in the leg, which may be felt only when standing or walking; increased warmth in the affected leg; red or discolored skin on the leg.
Symptoms of PE can include: sudden onset of unexplained shortness of breath or rapid breathing; sudden coughing which may bring up blood; sharp chest pain which may increase with deep breathing; sense of anxiety; severe light headedness or dizziness; rapid or irregular heartbeat. Some of these symptoms (e.g., “shortness of breath”, “coughing”) are nonspecific and might be misinterpreted as more common or less severe events (e.g., respiratory tract infections).
The risk for arterial thromboembolism (ATE) in users of oral contraceptives with low estrogen content (<50 µg ethinyl estradiol) ranges from about 1 to 3 cases per 10,000 woman-years. An arterial thromboembolic event (ATE) can include cerebrovascular accident, vascular occlusion, or myocardial infarction (MI). Symptoms of a cerebrovascular accident can include: sudden numbness or weakness of the face, arm, or leg, especially on one side of the body; sudden confusion, trouble speaking or understanding; sudden trouble seeing in one or both eyes; sudden trouble walking, dizziness, loss of balance or coordination; sudden, severe or prolonged headache with no known cause; loss of consciousness or fainting with or without seizure. Other signs of vascular occlusion can include: sudden pain, swelling, and slight blue discoloration of an extremity; acute abdomen.
Symptoms of MI can include: pain, discomfort, pressure, heaviness, sensation of squeezing or fullness in the chest, arm, or below the breastbone; discomfort radiating to the back, jaw, throat, arm, stomach; fullness, indigestion or choking feeling; sweating, nausea, vomiting, or dizziness; extreme weakness, anxiety, or shortness of breath; rapid or irregular heartbeats.
Arterial thromboembolic events are life-threatening and may have a fatal outcome.
Other Risk Factors for Venous or Arterial Thromboembolism or of a Cerebrovascular Accident
Other generalized risk factors for venous or arterial thromboembolism include but are not limited to age, severe obesity (body mass index >30 kg/m2), a personal history, a positive family history (the occurrence of VTE/ATE in a direct relative at a relatively early age may indicate genetic predisposition) and systemic lupus erythematosus. If a hereditary or acquired predisposition for venous or arterial thromboembolism is suspected, the woman should be referred to a specialist for advice before deciding on any COC use. The risk of VTE/ATE may be temporarily increased with prolonged immobilization, major surgery, or trauma. In these situations, it is advisable to discontinue COC use (in the case of elective surgery at least four weeks in advance) and not to resume COC use until two weeks after complete remobilization. Also, patients with varicose veins and leg cast should be closely supervised. Other risk factors may include smoking (with heavier smoking and increasing age, the risk further increases, especially in women over 35 years of age), dyslipoproteinemia, hypertension, migraine, valvular heart disease, and atrial fibrillation.
Biochemical factors that may be indicative of hereditary or acquired predisposition for venous or arterial thrombosis include Activated Protein C (APC) resistance, hyperhomocysteinemia, antithrombin-III deficiency, protein C deficiency, protein S deficiency, antiphospholipid antibodies (anticardiolipin antibodies, lupus anticoagulant).
When considering risk/benefit, the physician should take into account that adequate treatment of a condition may reduce the associated risk of thrombosis and that the risk associated with pregnancy is higher than that associated with low-dose COCs (<0.05 mg ethinyl estradiol).
Hepatic/Biliary/Pancreatic
In some cases of elevated liver enzymes reported during clinical trials with YASMIN, a contributory role of YASMIN could not be ruled out. YASMIN is contraindicated in patients with active liver disease (see 2 Contraindications and 9.7 Drug-Laboratory Test Interactions).
Acute or chronic disturbances of liver function may necessitate the discontinuation of COC use until markers of liver function return to normal.
Jaundice
Patients who have had jaundice should be given oral contraceptives with great care and under close observation. Oral contraceptive-related cholestasis has been described in women with a history of pregnancy-related cholestasis. Women with a history of cholestasis may have the condition recur with subsequent hormonal contraceptive use.
The development of severe generalized pruritus or icterus requires that the medication be withdrawn until the problem is resolved.
If a patient develops jaundice that proves to be cholestatic in type, the use of oral contraceptives should not be resumed. In patients taking hormonal contraceptives, changes in the composition of the bile may occur, and an increased incidence of gallstones has been reported.
Gallbladder Disease
Patients taking oral contraceptives have a greater risk of developing gallbladder disease requiring surgery with the first year of use. The risk may double after 4 or 5 years.
Hepatic Nodules
Hepatic nodules (adenoma and focal nodular hyperplasia) have been reported, particularly in long-term users of oral contraceptives. Although these lesions are extremely rare, they have caused fatal intra-abdominal hemorrhage and should be considered in women presenting with an abdominal mass, acute abdominal pain, or evidence of intra-abdominal bleeding.
Hepatitis C
YASMIN must be discontinued prior to starting therapy with the Hepatitis C virus (HCV) combination drug regimen ombitasvir, paritaprevir, ritonavir, with or without dasabuvir (see 2 Contraindications and 9 Drug Interactions). During clinical trials with ombitasvir, paritaprevir, ritonavir, with and without dasabuvir, ALT elevations 5 to >20 times the upper limit of normal (ULN) were significantly more frequent in healthy female subjects and HCV infected women using ethinyl estradiol-containing medications such as COCs. YASMIN can be restarted approximately 2 weeks following completion of treatment with the HCV combination drug regimen.
Immune
Angioedema
Exogenous estrogens may induce or exacerbate symptoms of angioedema, in particular, in women with hereditary angioedema.
Monitoring and Laboratory Tests
Physical Examination and Follow-up
Before oral contraceptives are used, a thorough history and physical examination should be performed, including a blood pressure determination and the family case history carefully noted. In addition, disturbances of the clotting system must be ruled out if any members of the family have suffered from thromboembolic diseases (e.g., deep vein thrombosis, stroke, myocardial infarction) at a young age. Breasts, liver, extremities, and pelvic organs should be examined, and a Papanicolaou (PAP) smear should be taken if the patient has been sexually active.
The first follow-up visit should be done three months after oral contraceptives are prescribed. Thereafter, examinations should be performed at least once a year, or more frequently if indicated. At each annual visit, examination should include those procedures that were done at the initial visit as outlined above or per recommendations of the Canadian Task Force on the Periodic Health Examination.
Neurologic
Migraine and Headache
The onset or exacerbation of migraine or the development of headache with a new pattern that is recurrent, persistent, or severe requires discontinuation of hormonal contraceptives and evaluation of the cause. Women with migraine headaches who take oral contraceptives may be at increased risk of stroke (see 2 Contraindications).
Ophthalmologic
Ocular Disease
Patients who are pregnant or are taking oral contraceptives may experience corneal edema that may cause visual disturbances and changes in tolerance to contact lenses, especially of the rigid type. Soft contact lenses usually do not cause disturbances. If visual changes or alterations in tolerance to contact lenses occur, temporary or permanent cessation of wear may be advised.
Ocular Lesions
There have been clinical case reports of retinal thrombosis associated with the use of oral contraceptives. Oral contraceptives should be discontinued if there is unexplained partial or complete loss of vision, onset of proptosis or diplopia, papilledema, or retinal vascular lesions. Appropriate diagnostic and therapeutic measures should be undertaken immediately.
Perioperative Considerations
There is an increased risk of thromboembolic complications in oral contraceptive users after major surgery. If feasible, oral contraceptives should be discontinued and an alternative method substituted at least one month prior to MAJOR elective surgery. Oral contraceptive use should not be resumed until the first menstrual period after hospital discharge following surgery.
Psychiatric
Patients with a history of emotional disturbances, especially the depressive type, may be more prone to have a recurrence of depression while taking oral contraceptives. In cases of a serious recurrence, a trial of an alternate method of contraception should be made, which may help to clarify the possible relationship. Women with premenstrual syndrome (PMS) may have a varied response to oral contraceptives, ranging from symptomatic improvement to worsening of the condition.
Renal
Fluid Retention
Hormonal contraceptives may cause some degree of fluid retention. They should be prescribed with caution and only with careful monitoring in patients with conditions which might be aggravated by fluid retention.
Reproductive Health
Fertility
After discontinuing oral contraceptive therapy, the patient should delay pregnancy until at least one normal spontaneous menstrual cycle has occurred in order to date the pregnancy. An alternate contraceptive method should be used during this time.
Amenorrhea
In some women, withdrawal bleeding may not occur during the tablet-free interval. If the COC has been taken according to directions, it is unlikely that the woman is pregnant. However, if the COC has not been taken according to directions prior to the first missed withdrawal bleed, or if two withdrawal bleeds are missed, pregnancy must be ruled out before COC use is continued.
Women having a history of oligomenorrhea, secondary amenorrhea, or irregular cycles may remain anovulatory or become amenorrheic following discontinuation of estrogen-progestin combination therapy.
Amenorrhea, especially if associated with breast secretion that continues for six months or more after withdrawal, warrants a careful assessment of hypothalamic-pituitary function.
Reduced Efficacy
The efficacy of COCs may be reduced in the event of missed tablets, gastro-intestinal disturbances, or concomitant medication (see 4 Dosage and Administration and 9 Drug Interactions).
Skin
Chloasma may occasionally occur with use of COCs, especially in women with a history of chloasma gravidarum. Women with a tendency to chloasma should avoid exposure to the sun or ultraviolet radiation while taking COCs.
7.1 Special Populations
7.1.1 Pregnancy
Oral contraceptives should not be taken by pregnant women. If pregnancy occurs during treatment with YASMIN, further intake must be stopped. However, if conception accidentally occurs while taking the pill, there is no conclusive evidence that the estrogen and progestin contained in the oral contraceptive will damage the developing child. One infant was born with esophageal atresia. A causal association with YASMIN is unknown.
7.1.2 Breastfeeding
In breastfeeding women, the use of oral contraceptives results in the hormonal components being excreted in breast milk and may reduce its quantity and quality. If the use of oral contraceptives is initiated after the establishment of lactation, there does not appear to be any effect on the quantity and quality of the milk. There is no evidence that low-dose oral contraceptives are harmful to the nursing infant.
If possible, the nursing mother should be advised not to use oral contraceptives, but to use other forms of contraception, until she has completely weaned her child.
After oral administration of YASMIN, about 0.02% of the drospirenone dose was excreted into the breast milk of postpartum women within 24 hours. This results in a maximal daily dose of about 3 µg drospirenone in an infant.
7.1.3 Pediatrics
The safety and efficacy of YASMIN has not been established in women under the age of 16 years. Use of this product before menarche is not indicated.
7.1.4 Geriatrics
YASMIN is not indicated for use in postmenopausal women.
8 Adverse Reactions
8.1 Adverse Reaction Overview
An increased risk of the following serious adverse reactions has been associated with the use of oral contraceptives:
- arterial and venous thromboembolism
- being diagnosed with breast cancer
- benign and malignant hepatic tumors
- cerebral hemorrhage
- cerebral thrombosis
- congenital anomalies
- gallbladder disease
- hypertension
- mesenteric thrombosis
- myocardial infarction
- neuro-ocular lesions (e.g., retinal thrombosis)
- pulmonary embolism
- thrombophlebitis
The following other adverse reactions also have been reported in patients receiving oral contraceptives: Nausea and vomiting, usually the most common adverse reaction, occurs in approximately 10% or fewer of patients during the first cycle.
The following other reactions, as a general rule, are seen less frequently or only occasionally:
- abdominal pain
- amenorrhea during and after treatment
- angioedema (exogenous estrogens may induce or exacerbate symptoms of angioedema in women with hereditary angioedema)
- auditory disturbances
- breakthrough bleeding
- breast changes (tenderness, enlargement, and secretion)
- cataracts
- changes in appetite
- change in corneal curvature (steepening)
- changes in libido
- change in menstrual flow
- change in weight (increase or decrease)
- changes in glucose tolerance or effect on peripheral insulin resistance
- chloasma or melasma which may persist
- cholestatic jaundice
- chorea
- Crohn’s disease
- cystitis-like syndrome
- mental depression
- diarrhea
- dizziness
- dysmenorrhea
- edema
- endocervical hyperplasia
- erythema multiforme
- erythema nodosum
- gallstone formationa
- gastrointestinal symptoms (such as abdominal cramps and bloating)
- headache
- hemolytic uremic syndromea
- hemorrhagic eruption
- herpes gestationisa
- hirsutism
- hypersensitivity
- hypertriglyceridemia (increased risk of pancreatitis when using COCs)
- hypertension
- impaired renal function
- increase in size of uterine leiomyomata
- intolerance to contact lenses
- jaundice related to cholestatisa
- liver function disturbances
- loss of scalp hair
- migraine
- nervousness
- optic neuritis
- otosclerosis-related hearing lossa
- pancreatitis
- porphyriaa
- possible diminution in lactation when given immediately postpartum
- premenstrual-like syndrome
- pruritis related to cholestasisa
- rash (allergic)
- Raynaud’s phenomenon
- reduced tolerance to carbohydrates
- retinal thrombosis
- rhinitis
- spotting
- Sydenham’s choreaa
- systemic lupus erythematosusa
- temporary infertility after discontinuation of treatment
- ulcerative colitis
- urticaria
- vaginal candidiasis
- vaginal discharge
- vaginitis
a Occurrence or deterioration of conditions for which association with COC use is not conclusive
8.2 Clinical Trial Adverse Reactions
Clinical trials are conducted under very specific conditions. The adverse reaction rates observed in the clinical trials; therefore, may not reflect the rates observed in practice and should not be compared to the rates in the clinical trials of another drug. Adverse reaction information from clinical trials may be useful in identifying and approximating rates of adverse drug reactions in real-world use.
The following are the most common adverse events reported with use of YASMIN during clinical trials, occurring in >1% of subjects and which may or may not be drug related: headache, menstrual disorder, breast pain, abdominal pain, nausea, leukorrhea, flu syndrome, acne, vaginal moniliasis, depression, diarrhea, asthenia, dysmenorrhea, back pain, infection, pharyngitis, intermenstrual bleeding, migraine, vomiting, dizziness, nervousness, vaginitis, sinusitis, cystitis, bronchitis, gastroenteritis, allergic reaction, urinary tract infection, pruritus, emotional lability, surgery, rash, upper respiratory infection.
8.3 Less Common Clinical Trial Adverse Reactions
Other reactions to oral contraceptives, as a general rule, are seen less frequently or only occasionally, as follows: gastrointestinal symptoms (such as abdominal cramps and bloating), breakthrough bleeding, spotting, change in menstrual flow, dysmenorrhea, amenorrhea during and after treatment, temporary infertility after discontinuation of treatment, edema, chloasma or melasma which may persist, breast changes (tenderness, enlargement, secretion), change in weight (increase or decrease), endocervical hyperplasias, possible diminution in lactation when given immediately postpartum, cholestatic jaundice, migraine, increase in size of uterine leiomyomata, rash (allergic), mental depression, reduced tolerance to carbohydrates, vaginal candidiasis, premenstrual-like syndrome, intolerance to contact lenses, change in corneal curvature (steepening), cataracts, optic neuritis, retinal thrombosis, changes in libido, chorea, changes in appetite, cystitis-like syndrome, rhinitis, headache, nervousness, dizziness, hirsutism, loss of scalp hair, erythema multiforme, erythema nodosum, hemorrhagic eruption, vaginitis, porphyria, impaired renal function, Raynaud’s phenomenon, auditory disturbances, hemolytic uremic syndrome, pancreatitis.
8.5 Post-Market Adverse Reactions
Cumulative postmarketing experience with YASMIN indicates a spontaneous reporting rate of venous thromboembolism of 5.1 events per 100 000 woman-years.
The following serious and unexpected adverse reactions have also been reported very rarely in users of YASMIN, but a causal relationship has not been established: pancytopenia, thrombocytopenia, arrhythmia, palpitations, tachycardia, ventricular extrasystoles, sudden hearing loss, ocular hypertension, visual disturbance, vitreous opacities, ischaemic colitis, hepatitis, hyperbilirubinemia, abnormal liver function test, decreased blood sodium, bone pain, pain in extremity, fibroadenoma of breast, seizure, dysarthria, facial paresis, hemiparesis, hypoesthesia, syncope, anxiety, nervousness, panic reaction, breast cyst, hematometra due to cervical polyp, asthma, leukocytoclastic vasculitis, lichen planus, and petechiae.
Cases of erythema nodosum, erythema multiforme, and hypersensitivity (including symptoms such as rash, urticaria) have been reported as adverse drug reactions from postmarket reporting in association with the use of YASMIN.
In addition, venous and arterial thromboembolic events (peripheral deep venous occlusion, thrombosis and embolism/pulmonary vascular occlusion, thrombosis, embolism and infarction/myocardial infarction/cerebral infarction and stroke not specified as hemorrhagic) have been identified as ADRs from postmarketing experience reported in association with the use of YASMIN (see 2 Contraindications and 7 Hematologic). Because these reactions are reported voluntarily from a population of uncertain size it is not always possible to reliably estimate their frequency or establish a causal relationship to drug exposure.
The following unexpected adverse events have also been reported very rarely in users of YASMIN; but a causal relationship has not been established: hot/cold sensations, muscle spasms, and muscle twitching.
Post-Market Active Surveillance Study
A prospective, controlled, noninterventional, active surveillance cohort study (EURAS) was conducted in Europe to compare risks of adverse cardiovascular and other events associated with the use of DRSP-containing OCs (YASMIN) and other OCs. In this study, 58,674 OC users were actively followed for a total of 142,475 woman-years. Loss to follow-up was 2.4%. The hazard ratios for venous thromboembolic (VTE) and for all thromboembolic (TE) events were close to 1 and thus do not suggest a higher risk for YASMIN users. The results exclude a 1.5 fold thromboembolic risk of YASMIN users compared to users of LNG-containing OCs and a 1.2-fold thromboembolic risk compared to users of other OCs. Arrhythmic events that could be suggestive of an increased serum potassium level (e.g., because of the antimineralocorticoid activity of DRSP) were not observed in this Postmarket Surveillance study.
Hazard ratios and confidence limits for VTE, ATE and TE are presented below in Table 3.
Table 3 – Adjusted Hazard Ratios (HR) and Confidence Limits for VTE, ATE and TE (As Treated Analysis)
| YASMIN vs | |||||||
|---|---|---|---|---|---|---|---|
| LNG-containing OCs | Other OCs | LNG and Other OCs | |||||
| HR | 95% CI | HR | 95% CI | HR | 95% CI | ||
| VTE | 1.05 | 0.61 – 1.81 | 0.77 | 0.48 – 1.26 | 0.87 | 0.55 – 1.37 | |
| ATE | 0.25 | 0.05 – 1.17 | 0.34 | 0.08 – 1.52 | 0.30 | 0.07 – 1.29 | |
| TEa | 0.85 | 0.51 – 1.42 | 0.69 | 0.44 – 1.12 | 0.76 | 0.49 – 1.17 | |
Abbreviations: ATE = arterial thromboembolism, CI = confidence interval, LNG = levonorgestrel, OC = oral contraception, TE = thromboembolic event, VTE = venous thromboembolism a All thromboembolic events (VTE and ATE combined) | |||||||
9 Drug Interactions
9.2 Drug Interactions Overview
The concurrent administration of oral contraceptives with other drugs may lead to breakthrough bleeding and/or may result in an altered response to either agent (see Table 4 and Table 5). Reduced effectiveness of the oral contraceptive, should it occur, is more likely with the low-dose formulations. It is important to ascertain all drugs that a patient is taking, both prescription and nonprescription, before oral contraceptives are prescribed.
9.3 Drug-Behaviour Interactions
See 7 Driving and Operating Machinery. No studies on the effects of YASMIN on the ability to drive or use machines have been performed.
9.4 Drug-Drug Interactions
The drugs listed in this table are based on either drug interaction case reports or studies, or potential interactions due to the expected magnitude and seriousness of the interaction (i.e., those identified as contraindicated).
Table 4 – Drugs Which May Decrease the Efficacy of Oral Contraceptives
| Class of Compound | Drug | Proposed Mechanism | Suggested Management |
|---|---|---|---|
| Class of Compound | Drug | Proposed Mechanism | Suggested Management |
| Antacids | Decreased intestinal absorption of progestins. | Dose two hours apart. | |
| Antibiotics | Ampicillin Cotrimoxazole Penicillin | Enterohepatic circulation disturbance, intestinal hurry. | For short course, use additional non-hormonal method of contraception or use another drug. For long course, use another non-hormonal method of contraception. |
| Antibiotics | Rifabutin Rifampin | Increased metabolism of progestins. Suspected acceleration of estrogen metabolism. | Use another non-hormonal method of contraception. |
| Antibiotics | Chloramphenicol Metronidazole Neomycin Nitrofurantoin Sulfonamides Tetracyclines | Induction of hepatic microsomal enzymes. Also disturbance of enterohepatic circulation. | For short course, use additional non-hormonal method of contraception or use another drug. For long course, use another non-hormonal method of contraception. |
| Antibiotics | Troleandomycin | May retard metabolism of oral contraceptives, increasing the risk of cholestatic jaundice. | For short course, use additional non-hormonal method of contraception or use another drug. For long course, use another non-hormonal method of contraception. |
| Anticonvulsants | Carbamazepine Ethosuximide Felbamate Lamotrigine Oxcarbazepine Phenobarbital Phenytoin Primidone Topiramate | Induction of hepatic microsomal enzymes. Rapid metabolism of estrogen and increased binding of progestin and ethinyl estradiol to SHBG. | Use higher dose oral contraceptives (50 μg ethinyl estradiol), another drug, or another non-hormonal method of contraception. |
| Antifungals | Griseofulvin | Stimulation of hepatic metabolism of contraceptive steroids may occur. | Use another non-hormonal method of contraception. |
| Cholesterol lowering agents | Clofibrate | Reduces elevated serum triglycerides and cholesterol; this reduces oral contraceptive efficacy. | Use another non-hormonal method of contraception. |
| HCV Protease Inhibitors | Boceprevir Telaprevir | Remains to be confirmed | Use another drug or another non-hormonal method of contraception. |
| HIV protease inhibitors | Ritonavir | Induction of hepatic microsomal enzymes. | Use another drug or another non-hormonal method of contraception. |
| Non-nucleoside reverse transcriptase inhibitors | Nevirapine | Induction of hepatic microsomal enzymes. | Use another drug or another non-hormonal method of contraception. |
| Sedatives and hypnotics | Barbiturates Benzodiazepines Chloral hydrate Glutethimide Meprobamate | Induction of hepatic microsomal enzymes. | For short course, use additional non-hormonal method of contraception or another drug. For long course, use another non-hormonal method of contraception or higher dose oral contraceptives. |
| Other drugs | Antihistamines Analgesics Antimigraine preparations Phenylbutazone preparations Vitamin E | Reduced oral contraceptive efficacy has been reported. Remains to be confirmed. |
Enzyme induction can already be observed after a few days of treatment. Maximal enzyme induction is generally seen within a few weeks. After the cessation of drug therapy enzyme induction may be sustained for about 4 weeks.
Women on short-term treatment with any of these drugs should temporarily use a barrier method in addition to the COC or choose another method of contraception. The barrier method should be used during the time of concomitant drug administration and for 28 days after their discontinuation. If the period during which the barrier method is used runs beyond the end of the tablets in the COC pack, the next COC pack should be started without the usual tablet-free interval.
For women on long-term treatment with hepatic enzyme-inducing active substances, another reliable, non-hormonal, method of contraception is recommended.
Several of the anti-HIV/HCV protease inhibitors (e.g., ritonavir, telaprevir, boceprevir) and non-nucleoside reverse transcriptase inhibitors (e.g., nevirapine) have been studied with co-administration of oral combination hormonal contraceptives; significant changes (increase or decrease) in the mean AUC of the estrogen or progestogen have been noted in some cases. The efficacy and safety of oral contraceptive products may be affected. Healthcare professionals should refer to the label of the individual anti-HIV/HCV protease inhibitor for further drug-drug interaction information.
Strong and moderate CYP3A4 inhibitors such as azole antifungals (e.g., ketoconazole, itraconazole, voriconazole, fluconazole), verapamil, macrolides (e.g., clarithromycin, erythromycin), diltiazem and grapefruit juice, can increase plasma concentrations of the estrogen or the progestin or both. Increase in DRSP may increase serum potassium levels, possibly increasing the risk of hyperkalemia in high-risk patients (see 7 General).
Oral contraceptives may also interfere with the metabolism of other drugs (see Table 5). Accordingly, plasma and tissue concentrations may either increase (e.g., cyclosporine) or decrease (e.g., lamotrigine).
Table 5 – Modification of Other Drug Action by Oral Contraceptives
| Class of Compound | Drug | Modification of Drug Action | Suggested Management |
|---|---|---|---|
| Class of Compound | Drug | Modification of Drug Action | Suggested Management |
| Alcohol | Possible increased levels of ethanol or acetaldehyde. | Use with caution. | |
Alpha-II adrenoreceptor agents | Clonidine | Sedation effect increased. | Use with caution. |
| Anticoagulants | All | Oral contraceptives increase clotting factors, decrease efficacy. However, oral contraceptives may potentiate action in some patients. | Use another non-hormonal method of contraception. |
| Anticonvulsants | All | Fluid retention may increase risk of seizures. | Use another non-hormonal method of contraception. |
| Lamotrigine | Decreased lamotrigine levels, may lead to breakthrough seizures | Use another non-hormonal method of contraception. | |
| Antidiabetic drugs | Oral hypoglycemics and insulin | Oral contraceptives may impair glucose tolerance and increase blood glucose. | Use low-dose estrogen and progestin oral contraceptive or another non-hormonal method of contraception. Monitor blood glucose. |
| Antihypertensive agents | Guanethidine and methyldopa | Estrogen component causes sodium retention, progestin has no effect. | Use low-dose estrogen oral contraceptive or use another non-hormonal method of contraception. |
| Beta blockers | Increased drug effect (decreased metabolism). | Adjust dose of drug if necessary. Monitor cardiovascular status. | |
| Antipyretics | Acetaminophen | Increased metabolism and renal clearance. | Dose of drug may have to be increased. |
| Antipyretics | Antipyrine | Impaired metabolism. | Decrease dose of drug. |
| Antipyretics | ASA | Effects of ASA may be decreased by the short-term use of oral contraceptives. | Patients on chronic ASA therapy may require an increase in ASA dosage. |
| Aminocaproic acid | Theoretically, a hypercoagulable state may occur because oral contraceptives augment clotting factors. | Avoid concomitant use. | |
| Betamimetic agents | Isoproterenol | Estrogen causes decreased response to these drugs. | Adjust dose of drug as necessary. Discontinuing oral contraceptives can result in excessive drug activity. |
| Caffeine | The actions of caffeine may be enhanced as oral contraceptives may impair the hepatic metabolism of caffeine. | Use with caution. | |
| Cholesterol-lowering agents | Clofibrate | Its action may be antagonized by oral contraceptives. Oral contraceptives may also increase metabolism of clofibrate. | May need to increase dose of clofibrate. |
| Corticosteroids | Prednisone | Markedly increased serum levels. | Possible need for decrease in dose. |
| Cyclosporine | May lead to an increase in cyclosporine levels and hepatotoxicity. | Monitor hepatic function. The cyclosporine dose may have to be decreased. | |
| Direct-acting antiviral (DAA) medicinal products | Ombitasvir, Paritaprevir, Ritonavir, with and without Dasabuvir | Has been shown to be associated with increases in ALT levels 5 to > 20 times the upper limit of normal in healthy female subjects and HCV infected women | See 2 Contraindications and 7 Hepatic/Biliary/Pancreatic |
| Folic acid | Oral contraceptives have been reported to impair folate metabolism. | May need to increase dietary intake, or supplement. | |
| Meperidine | Possible increased analgesia and CNS depression due to decreased metabolism of meperidine. | Use combination with caution. | |
| Phenothiazine tranquilizers | All phenothiazines, reserpine, and similar drugs | Estrogen potentiates the hyperprolactinemia effect of these drugs. | Use other drugs or lower-dose oral contraceptives. If galactorrhea or hyperprolactinemia occurs, use other non-hormonal method of contraception. |
| Sedatives and hypnotics | Chlordiazepoxide Diazepam Lorazepam Oxazepam | Increased effect (increased metabolism). | Use with caution. |
| Theophylline | All | Decreased oxidation, leading to possible toxicity. | Use with caution. Monitor theophylline levels. |
| Tricyclic antidepressants | Clomipramine (possibly others) | Increased side effects: e.g., depression | Use with caution. |
| Vitamin B12 | Oral contraceptives have been reported to reduce serum levels of Vitamin B12 | May need to increase dietary intake, or supplement. |
In clinical studies, administration of a hormonal contraceptive containing ethinyl estradiol did not lead to any increase or only to a weak increase in plasma concentrations of CYP3A4 substrates (e.g., midazolam) while plasma concentrations of CYP1A2 substrates can increase weakly (e.g., theophylline) or moderately (e.g., melatonin and tizanidine).
Interactions With Drugs That Have the Potential to Increase Serum Potassium
There is a potential for an increase in serum potassium in women taking YASMIN with other drugs (see 7 Warnings and Precautions). Of note, occasional or chronic use of NSAID medication was not restricted in any of the YASMIN clinical trials.
A drug-drug interaction study of DRSP 3 mg/estradiol (E2) 1 mg versus placebo was performed in 24 mildly hypertensive postmenopausal women taking enalapril maleate 10 mg twice daily. Potassium levels were obtained every other day for a total of 2 weeks in all subjects. Mean serum potassium levels in the DRSP/E2 treatment group relative to baseline were 0.22 mEq/L higher than those in the placebo group. Serum potassium concentrations also were measured at multiple timepoints over 24 hours at baseline and on Day 14. On Day 14, the ratios for serum potassium Cmax and AUC in the DRSP/E2 group to those in the placebo group were 0.955 (90% CI: 0.914, 0.999) and 1.010 (90% CI: 0.944, 1.080), respectively. No patient in either treatment group developed hyperkalemia (serum potassium concentrations >5.5 mEq/L).
Metabolic Interactions
Drospirenone
Metabolism of drospirenone (DRSP) and potential effects of DRSP on hepatic cytochrome P450 (CYP) enzymes have been investigated in in vitro and in vivo studies (see 10.3 Pharmacokinetics). In in vitro studies, DRSP did not affect turnover of model substrates of CYP1A2 and CYP2D6, but had an inhibitory influence on the turnover of model substrates of CYP1A1, CYP2C9, CYP2C19, and CYP3A4, with CYP2C19 being the most sensitive enzyme. The potential effect of DRSP on CYP2C19 and CYP3A4 activity was investigated in clinical pharmacokinetic studies using omeprazole, simvastatin and midazolam as marker substrates. In a study with 24 postmenopausal women (including 12 women with homozygous [wild type] CYP2C19 genotype and 12 women with heterozygous CYP2C19 genotype), the daily oral administration of 3 mg DRSP for 14 days did not affect the oral clearance of omeprazole (40 mg, single oral dose). Two additional clinical drug-drug interaction studies using simvastatin and midazolam as marker substrates for CYP3A4 were each performed in 24 healthy postmenopausal women. The results of these studies demonstrated that pharmacokinetics of the CYP3A4 substrates were not influenced by steady state DRSP concentrations achieved after administration of 3 mg DRSP/day. Based on the available results of in vivo and in vitro studies, it can be concluded that, at clinical dose level, DRSP shows little propensity to interact to a significant extent with cytochrome P450 enzymes.
Ethinyl estradiol
In vitro, ethinyl estradiol is a reversible inhibitor of CYP2C19, CYP1A1 and CYP1A2 as well as a mechanism based inhibitor of CYP3A4/5, CYP2C8, and CYP2J2.
9.5 Drug-Food Interactions
Interactions with food have not been established.
9.6 Drug-Herb Interactions
Herbal products containing St. John’s wort (hypericum perforatum) may induce hepatic enzymes (cytochrome P450) and p-glycoprotein transporter and may reduce the effectiveness of contraceptive steroids. This may also result in breakthrough bleeding.
9.7 Drug-Laboratory Test Interactions
Results of laboratory tests should be interpreted with the knowledge that the patient is taking an oral contraceptive. The following laboratory tests are modified:
Liver Function Tests
Aspartate serum transaminase (AST) - variously reported elevations
Alkaline phosphatase and gamma glutamine transaminase (GGT) - slightly elevated
Coagulation Tests
Minimal elevation of test values reported for such parameters as prothrombin and factors VII, VIII, IX, and X.
Thyroid Function Tests
Protein binding of thyroxine is increased as indicated by increased total serum thyroxine concentrations and decreased T3 resin uptake.
Lipoproteins
Small changes of unproven clinical significance may occur in lipoprotein cholesterol fractions.
Gonadotropins
LH and FSH levels are suppressed by the use of oral contraceptives. Wait two weeks after discontinuing the use of oral contraceptives before measurements are made.
Glucose Tolerance
Oral glucose tolerance remained unchanged or was slightly decreased.
Tissue Specimens
Pathologists should be advised of oral contraceptive therapy when specimens obtained from surgical procedures and Pap smears are submitted for examination.
10 Clinical Pharmacology
10.1 Mechanism of Action
YASMIN is a monophasic, combination oral contraceptive that contains the active ingredients drospirenone and ethinyl estradiol. Combination oral contraceptives act by suppression of gonadotropins. Although the primary mechanism of this action is inhibition of ovulation, other alterations include changes in the cervical mucus (which increases the difficulty of sperm entry into the uterus) and the endometrium (which reduces the likelihood of implantation).
Drospirenone is a spironolactone analogue with antimineralocorticoid activity. Preclinical studies in animals and in vitro have shown that drospirenone has no androgenic, estrogenic, glucocorticoid and antiglucocorticoid activity. Preclinical studies in animals have also shown that drospirenone has antiandrogenic activity.
Estrogen-containing combinations such as YASMIN increase the blood level of sex hormone binding-globulin (SHBG), which is capable of binding and thus inactivating androgens such as testosterone. Moreover, the anti-androgenic activity of drospirenone partially counteracts the effects of endogenous androgens, blocking the binding of dihydrotestosterone (DHT) at the receptor level, which makes it a suitable option in the treatment of acne. Drospirenone may also help to reduce edema of the wall of the sebaceous follicle during the second half of the menstrual cycle, which is partly responsible for the flare-up of inflammatory lesions at this cycle phase.
10.2 Pharmacodynamics
Drospirenone inhibits ovulation and follicular development at an oral threshold dose of 2 mg. Drospirenone 3 mg, in combination with ethinyl estradiol 0.03 mg, was found to be optimal for inhibition of ovulation and cycle control.
Drospirenone exhibited aldosterone antagonist activity at doses as low as 2 mg/day in healthy volunteers. Plasma renin activity and plasma aldosterone concentrations were increased, as was the excretion of aldosterone metabolites. The excretion of Na+ was transiently increased by drospirenone (2 or 3 mg) alone or in combination with ethinyl estradiol (0.03 mg). Serum Na+ and K+ concentrations remained unchanged. The potency of drospirenone was 6.6 times higher on average than that of spironolactone, using the Na+/K+ urinary ratio as the primary indicator of potency of the aldosterone antagonistic effect.
Drospirenone (2, 3, or 4 mg) in combination with ethinyl estradiol (0.03 mg) displayed a favourable effect on the lipid profile with an increase in HDL and a slight decrease in LDL. Total cholesterol remained unchanged. In addition, oral glucose tolerance remained unchanged or was slightly decreased.
Drospirenone had no effect on the biosynthesis of sex hormone binding globulin (SHBG) and when administered in conjunction with ethinyl estradiol (0.03 mg), resulted in SHBG and corticosteroid binding globulin increases consistent with the dosage of ethinyl estradiol.
In vitro, drospirenone bound with low affinity to SHBG and did not bind at all to corticosteroid binding globulin (CBG).
10.3 Pharmacokinetics
Table 6 – Mean Pharmacokinetic Parameters of YASMIN (Drospirenone 3 mg and Ethinyl Estradiol 0.03 mg)
Drospirenone Mean (%CV) Values | |||||
|---|---|---|---|---|---|
| Cycle/Day | No. of Subjects | Cmax (ng/mL) | tmax (h) | AUC(0-24h) (ng·h/mL) | t½ (h) |
| 1/1 | 12 | 36.9 (13) | 1.7 (47) | 288 (25) | NA |
| 1/21 | 12 | 87.5 (59) | 1.7 (20) | 827 (23) | 30.9 (44) |
| 6/21 | 12 | 84.2 (19) | 1.8 (19) | 930 (19) | 32.5 (38) |
| 9/21 | 12 | 81.3 (19) | 1.6 (38) | 957 (23) | 31.4 (39) |
| 13/21 | 12 | 78.7 (18) | 1.6 (26) | 968 (24) | 31.1 (36) |
Ethinyl Estradiol Mean (%CV) Values | |||||
| Cycle/Day | No. of Subjects | Cmax (pg/mL) | tmax (h) | AUC(0-24h) (pg·h/mL) | t½ (h) |
| 1/1 | 11 | 53.5 (43) | 1.9 (45) | 280.3 (87) | NA |
| 1/21 | 11 | 92.1 (35) | 1.5 (40) | 461.3 (94) | NA |
| 6/21 | 11 | 99.1 (45) | 1.5 (47) | 346.4 (74) | NA |
| 9/21 | 11 | 87.0 (43) | 1.5 (42) | 485.3 (92) | NA |
| 13/21 | 10 | 90.5 (45) | 1.6 (38) | 469.5 (83) | NA |
| NA = Not available | |||||
Absorption:
The absolute bioavailability of drospirenone (DRSP) from a single entity tablet is about 76%. The absolute bioavailability of ethinyl estradiol (EE) is approximately 40% as a result of presystemic conjugation and first-pass metabolism. The absolute bioavailability of YASMIN which is a combination tablet of drospirenone and ethinyl estradiol has not been evaluated. Serum concentrations of DRSP and EE reached peak levels within 1-3 hours after administration of YASMIN. After single-dose administration of YASMIN, the relative bioavailability, compared to a suspension, was 107% and 117% for DRSP and EE, respectively.
The pharmacokinetics of DRSP are dose proportional following single doses ranging from 1 10 mg. Following daily dosing of YASMIN, steady state DRSP concentrations were observed after 10 days. There was about 2- to 3-fold accumulation in serum Cmax and AUC(0-24h) values of DRSP following multiple-dose administration of YASMIN (see Table 6).
For EE, steady-state conditions are reported during the second half of a treatment cycle. Following daily administration of YASMIN, serum Cmax and AUC(0-24h) values of EE accumulate by a factor of about 1.5 to 2.0.
Effect of Food
The rate of absorption of DRSP and EE following single administration of two YASMIN tablets was slower under fed conditions, with the serum Cmax being reduced about 40% for both components. The extent of absorption of DRSP, however, remained unchanged. In contrast, the extent of absorption of EE was reduced by about 20% under fed conditions.
Distribution:
DRSP and EE serum levels decline in two phases. The apparent volume of distribution of DRSP is approximately 4 L/kg and that of EE is reported to be approximately 4 5 L/kg.
DRSP does not bind to sex hormone-binding globulin (SHBG) or corticosteroid-binding globulin (CBG) but binds about 97% to other serum proteins. Multiple dosing over 3 cycles resulted in no change in the free fraction (as measured at trough levels). EE is reported to be highly, but nonspecifically, bound to serum albumin (approximately 98.5%) and induces an increase in the serum concentrations of both SHBG and CBG. EE-induced effects on SHBG and CBG were not affected by variation of the DRSP dosage in the range of 2 to 3 mg.
Metabolism:
The two main metabolites of DRSP found in human plasma were identified to be the acid form of DRSP, generated by opening of the lactone ring, and the 4,5-dihydrodrospirenone-3-sulfate, formed by reduction and subsequent sulfation. These metabolites were shown not to be pharmacologically active. DRSP is also subject to oxidative metabolism catalyzed by CYP3A4.
EE is subject to significant gut and hepatic first-pass metabolism. EE and its oxidative metabolites are primarily conjugated with glucuronides or sulfate. CYP3A4 in the liver are responsible for the 2 hydroxylation which is the major oxidative reaction. The 2-hydroxy metabolite is further transformed by methylation and glucuronidation prior to urinary and fecal excretion.
Elimination:
DRSP serum levels are characterized by a terminal disposition phase half-life of approximately 30 hours after both single- and multiple-dose regimens. Excretion of DRSP was nearly complete after ten days and amounts excreted were slightly higher in feces compared to urine. DRSP was extensively metabolized and only trace amounts of unchanged DRSP were excreted in urine and feces. At least 20 different metabolites were observed in urine and feces. About 38% to 47% of the metabolites in urine were glucuronide and sulfate conjugates. In feces, about 17% to 20% of the metabolites were excreted as glucuronides and sulfates.
For EE, the terminal disposition phase half-life has been reported to be approximately 24 hours. EE is not excreted unchanged. EE is excreted in the urine and feces as glucuronide and sulfate conjugates and undergoes enterohepatic circulation.
Special populations and conditions
- Pediatrics (<16 years of age): There is no PK data available. Use of this product before menarche is not indicated.
- Geriatrics: There is no PK data available. YASMIN is not indicated for use in postmenopausal women.
- Sex: Yasmin is intended for use only in women of reproductive age.
Pregnancy and breastfeeding:
- Pregnancy: YASMIN is not indicated for use in pregnancy (see 2 Contraindications and 7.1.1 Pregnancy).
- Breastfeeding: There does not appear to be any effect on the quantity and quality of the milk. There is no evidence that low-dose oral contraceptives are harmful to the nursing infant (see 7.1.2 breastfeeding).
- Ethnic Origin: The effect of race on the disposition of YASMIN has not been evaluated.
- Hepatic Insufficiency: YASMIN is contraindicated in patients with hepatic dysfunction (see 7 Hepatic/Biliary/Pancreatic). The mean terminal half-life of DRSP for women with moderate hepatic impairment was 1.8 times greater than for women with normal hepatic function.
Renal Insufficiency: YASMIN is contraindicated in patients with renal insufficiency (see 7 Renal).
The effect of renal insufficiency on the pharmacokinetics of DRSP (3 mg daily for 14 days) and the effect of DRSP on serum potassium levels were investigated in female subjects (n=28, age 30-65) with normal renal function and mild and moderate renal impairment. All subjects were on a low potassium diet. During the study, 7 subjects continued the use of potassium-sparing drugs for the treatment of the underlying illness. On the 14th day (steady-state) of DRSP treatment, the serum DRSP levels in the group with mild renal impairment (creatinine clearance CLcr, 50 80 mL/min) were comparable to those in the group with normal renal function (CLcr, >80 mL/min). The serum DRSP levels were on average 37% higher in the group with moderate renal impairment (CLcr, 30-50 mL/min) compared to those in the group with normal renal function. DRSP treatment was well tolerated by all groups. DRSP treatment did not show any clinically significant effect on serum potassium concentration. Although hyperkalemia was not observed in the study, in five of the seven subjects who continued use of potassium-sparing drugs during the study, mean serum potassium levels increased by up to 0.33 mEq/L. Therefore, potential exists for hyperkalemia to occur in subjects with renal impairment whose serum potassium is in the upper reference range and who are concomitantly using potassium sparing drugs.
11 Storage, Stability, and Disposal
Store in original packaging between 15°C and 30°C.
Medicines should not be disposed of via wastewater or household waste. Ask your pharmacist how to dispose of medicines no longer required. These measures will help to protect the environment.
Part 2: Scientific Information
13 Pharmaceutical Information
Drug Substance
Drospirenone
| Non-proprietary name of the drug substance: | Drospirenone |
|---|---|
| Chemical name: | 6β, 7β; 15β, 16β-dimethylene-3-oxo-17α-pregn-4-ene-21, 17-carbolactone (IUPAC) [6R-(6α, 7α, 8β, 9α, 10β, 13β, 14α, 15α, 16α, 17β]-1,3',4',6, 7,8,9,10,11,12,13,14,15,16,20,21-hexadecahydro-10,13-dimethylspiro[17H-dicyclopropa[6,7:15, 16] cyclopenta[α]phenanthrene-17,2'(5'H)-furan]-3,5'(2H)-dione (USAN) |
| Molecular formula: | C24H30O3 |
| Structural formula: | |
| Molecular weight: | 366.50 |
| Description: | White to off-white crystalline powder. Freely soluble in dichloromethane; soluble in acetone, methanol, ethyl acetate, dimethoxyethane, and toluene; sparingly soluble in ethanol, and practically insoluble in water, n-hexane and diisopropyl ether. Melting range is 199°C to 201°C. |
| pKa: | Neutral molecule without any acid-base properties in aqueous solutions (pH 1 to 12) |
| Partition coefficient: | log POW = 3.08 |
Ethinyl estradiol
| Non-proprietary name of the drug substance: | ethinyl estradiol |
|---|---|
| Chemical name: | 19-nor-17α-pregna-1,3,5(10)-triene-20-yne-3,17-diol (IUPAC) |
| Molecular formula: | C20H24O2 |
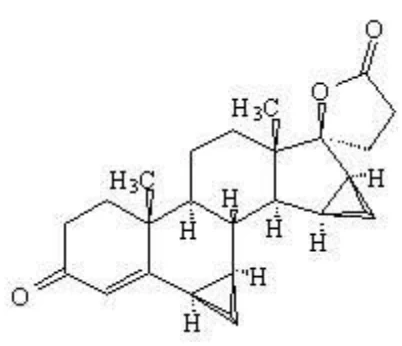 |
| Structural formula: | 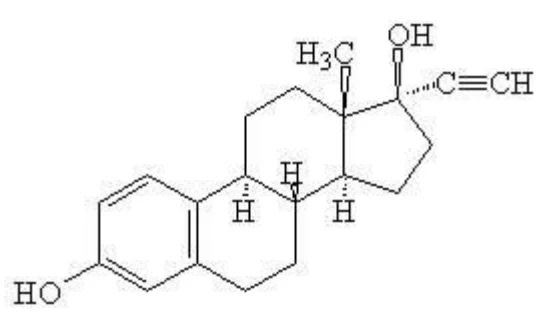 |
|---|---|
| Molecular weight: | 296.41 |
| Description: | White to yellowish-white crystals or crystalline powder. Freely soluble in ether, ethanol, acetone, and dioxane; soluble in chloroform and alkali hydroxide solutions; practically insoluble in water. Melting range is 181°C to 185°C. |
| pKa: | 10.25 ± 0.04 |
| Partition coefficient: | log POW = 4.17 ± 0.03 (pH=5) 4.20 ± 0.04 (pH=7) 4.15 ± 0.04 (pH=9) |
14 Clinical Trials
14.1 Clinical Trial by Indication
Oral Contraception
The contraceptive efficacy of YASMIN (drospirenone and ethinyl estradiol) was demonstrated in three pivotal, open-label, multicentre, clinical trials conducted in women 16 to 40 years of age (see Table 7).
Table 7 – Contraceptive Efficacy of YASMIN in 3 Pivotal Clinical Trials
| Study 1 | Study 2 | Study 3 | |||||
|---|---|---|---|---|---|---|---|
| Correcteda Pearl Index | |||||||
| Number of cycles | 3192 | 18418 | 9490 | ||||
| Number of pregnancies | 1 | 10 | 3 | ||||
| Pearl Index | 0.41 | 0.71 | 0.41 | ||||
| Correcteda Pregnancy Ratio | |||||||
| Cycles completed/subject | 13 | 13 | 26 | ||||
| Number of subjects | 220 | 1186 | 268 | ||||
| Number of pregnancies | 1 | 10 | 3 | ||||
| Pregnancy Ratio (%) | 0.46 | 0.84 | 1.18 | ||||
| a Corrected to exclude concomitant use of other contraceptives | |||||||
Of the 14 on-treatment pregnancies reported for YASMIN, there were 11 cases in which co factors (missed tablets, diarrhea, etc) were identified that could have reduced the contraceptive efficacy. These cases may be accepted as user failures.
Acne Therapy
The efficacy of YASMIN in treating moderate acne was demonstrated in two pivotal, double blind, comparative, multicentre clinical trials in women 16 to 40 years of age.
Study A07158
The primary objectives of the study were to compare the efficacy of YASMIN with a triphasic preparation containing 0.035 mg ethinyl estradiol and 0.180, 0.215, 0.250 mg norgestimate (EE/NGM), in terms of relative change in inflammatory lesion count in percent (papules + pustules + nodules), relative changes in total lesion count in percent (papules + pustules + nodules + open and closed comedones), and the proportion of subjects who showed improvement of their facial acne according to the investigator’s global assessment from randomization to Cycle 6.
Female subjects were randomized to YASMIN (n = 568) or EE/NGN (n = 586) for 6 treatment cycles.
The relative change (reduction) from baseline to Cycle 6 in mean percentage inflammatory lesion count was 73.4% for YASMIN vs 71.0% in EE/NGM (P value of one-sided t-test for noninferiority is smaller than 0.001) for the full analysis set population.
The relative change (reduction) from baseline to Cycle 6 in the mean percentage total lesion count was 67.6% in YASMIN and 64.3% in EE/NGM for the full analysis set population.
For the investigator’s global assessment, improvement of facial acne was observed in subjects treated with YASMIN (95.6%) vs EE/NGM (92.1%) for the full analysis set population.
The per protocol analysis showed similar results to the full analysis set.
Study AM80
This multicentre, double-blind, randomized study compared the effect of YASMIN with that of 0.035 mg ethinyl estradiol/2 mg cyproterone acetate (EE/CPA). The study was completed over 9 treatment cycles. A total of 128 women with acne (aged 16-33 with a minimum of 8 papulopustular lesions on the face) were randomized. Treatment with either YASMIN (n = 82) or EE/CPA (n = 43) was assigned in a 2:1 ratio. Acne lesion count was assessed as the primary variable. After nine treatment cycles, the mean number of acne lesions was reduced by 37.51% in the YASMIN group and 35.03% in the EE/CPA group in the intent-to-treat (ITT) population (P value from Wilcoxon test = 0.0006).
The per protocol analysis showed similar results to the ITT analysis.
16 Non-Clinical Toxicology
General toxicity
The long-term toxicity of drospirenone, alone and in combination with ethinyl estradiol, was investigated after daily intragastric administration of the following doses.
Table 8 – Long-term Toxicity Studies Conducted With Drospirenone (DRSP) and Ethinyl Estradiol (EE)
| Species | No./Group | Dose (mg/kg/day) | Treatment Period | ||
|---|---|---|---|---|---|
| DRSP+EE | DRSP Alone | EE Alone | |||
| Rat | 25F | -- | 0, 0.6, 3, 15 | -- | 27 weeks |
| Rat | 20F | 0+0, 0.3+0.003, 3+0.03, 10+0.1 | -- | -- | 52-53 weeks |
| Monkey | 4F | -- | 0, 0.2, 2, 10 | -- | 27 weeks |
| Monkey | 4-5F | 0+0, 0.3+0.03, 3+0.3, 10+1 | 3, 1.0 | 0.03, 0.1 | 53-54 weeks |
Compound-related findings were generally limited to pharmacologic and exaggerated pharmacologic effects expected following administration of an exogenous progestogen or estrogen/progestogen combination. No organ toxicity was observed.
Changes observed following administration of drospirenone alone included:
- alterations in lipid, carbohydrate and protein metabolism (rats: ≥1 mg/kg/day)
- increased body weight gain and food consumption (rats: ≥3 mg/kg/day)
- decreased liver weights accompanied by decreased hepatic glycogen content (monkeys: ≥2 mg/kg/day)
- increased liver weights accompanied by increased hepatic DNA and protein content (rats: ≥50 mg/kg/day)
- changes in electrolyte excretion (rats: ≥10 mg/kg/day; monkeys: 10 mg/kg/day)
- decreased ovarian weights (mice: 30 mg/kg/day)
- decreased (mice: 30 mg/kg/day) or slightly increased (monkeys: 10 mg/kg/day) adrenal gland weights
- microscopic changes in endocrine target organs (mice: ≥3 mg/kg/day; rats: ≥3 mg/kg/day; monkeys: ≥0.2 mg/kg/day)
A spectrum of compound-related estrogenic, progestogenic and antimineralocorticoid effects was observed following administration of the combination to female mice, rats, and monkeys. In addition, the antagonism of some estrogenic effects (decreased body weight and food consumption [rats];
hematologic changes [rats, monkeys], and increased uterine weights [mice]), and antagonism of some progestogenic effects (increased body weight and food consumption [rats]) were observed.
Synergism of other effects was observed in mice and rats and included atrophy of ovarian interstitial glands, decreased luteal mass and sexual cycles in mice, and decreased ovarian weights and increased hepatic N-demethylase activity in rats. In comparison with administration of either substance alone, administration of the combination to rats and cynomolgus monkeys eliminated some single substance effects (alterations in hepatic cytochrome P450 content). Overt toxicity was limited to one possible compound-related death in cynomolgus monkeys administered the combination at a dose of 3 mg/kg drospirenone + 0.03 mg/kg ethinyl estradiol for 11 weeks.
Toxicokinetic monitoring showed that on the basis of AUC(0-24h) values, the highest doses used in mice (30 mg/kg/day), rats (15 mg/kg/day), and monkeys (10 mg/kg/day) which did not produce overt signs of toxicity led to roughly 10.6 times (mice), >12 times (rats), and ca 22 times (monkeys) higher systemic exposure as compared to human exposure at the therapeutic dose.
Genotoxicity
No mutagenic effect of drospirenone was demonstrated in vitro in bacterial (Salmonella typhimurium, Escherichia coli) or mammalian (human lymphocyte, Chinese hamster) cells in the presence or absence of extrinsic metabolic activation. Drospirenone did not increase the occurrence of micronucleated red blood cells in vivo following single intragastric administration of 1000 mg/kg to mice.
Drospirenone increased unscheduled DNA synthesis in primary hepatocytes of female rats in vitro in a dose-dependent manner at a concentration of 10 to 60 μg/mL. Intragastric administration of drospirenone 10 mg/kg/day to rats for 14 consecutive days generated two forms of DNA adducts in male and female rat livers. Low levels of three compound-related DNA adducts were also observed in the livers of female mice given drospirenone 10 mg/kg/day, alone or in combination with 0.1 mg/kg/day ethinyl estradiol, in the carcinogenicity study. In contrast to these findings observed in rodent livers, results from an in vitro study conducted with drospirenone 5 μg/mL in human liver slices did not indicate a DNA adduct forming potential of drospirenone in human tissue. Given the lack of any drospirenone-related liver tumor formation in mice and rats, the biological relevance of this interaction with DNA in the rodent liver with regard to risk assessment in humans is questionable.
Carcinogenicity
The carcinogenic potential of drospirenone, alone and in combination with ethinyl estradiol, was investigated in female mice and rats.
No carcinogenicity was observed after two years of treatment with drospirenone as a single compound in mice or rats. Mortality was increased in rats at the highest dose of drospirenone. The increased food intake of the rats with a resultant increase in body weight was considered as the reason for the reduction in their life span. In the mouse study there were no effects on the survival of the animals observed after treatment with drospirenone.
Tumorigenic effects of the drug combination in mice were manifested by an increased incidence of pituitary adenomas at all doses, overall mammary tumors at the mid and low doses, and uterine adenocarcinomas at the mid and high doses in comparison with controls. The same qualitative tumor pattern (however, quantitatively more pronounced, especially in the pituitary) was seen in groups treated with ethinyl estradiol alone. As drospirenone alone elicited no tumorigenic response, the tumorigenic potential of the combination was attributed to ethinyl estradiol.
Treatment of rats with the drug combination resulted in an increased incidence of hepatic adenomas at the high dose and of total liver tumors from the mid dose onwards. A similar effect on liver tumor induction was seen in groups receiving ethinyl estradiol alone. Therefore, this effect on the liver could be attributed to the activity of ethinyl estradiol.
Compared to the control group, a tendency towards an increased rate of endometrial adenoma with a concomitant decrease in the rate of adenocarcinoma was seen in the uteri from the animals of the low-dose combination group. In the mid- and high-dose combination groups, no endometrial adenomas or adenocarcinomas were noted, i.e., there was a reduction in the rate of uterine tumors below the control level. A clear-cut increase in these uterine tumor incidences was induced by ethinyl estradiol when given alone from the mid dose onwards. Thus, the presence of drospirenone in the drug combination apparently led to a suppression of the deleterious estrogenic effect on the uterus. Treatment with ethinyl estradiol at the high dose led to an increased incidence of adenocarcinoma in the mammary glands. This effect was also completely counteracted by drospirenone in the drug combination group.
Reproductive and developmental toxicology:
The reproductive toxicity of drospirenone, alone and in combination with ethinyl estradiol, was investigated in rats, rabbits, and monkeys.
As expected from the pharmacological activity of an estrogen/progestogen combination, estrous cycle disturbances and a transient impairment of fertility were observed in rats when treated for 6 weeks prior to mating with doses of 5 mg/kg/day drospirenone + 0.05 mg/kg/day ethinyl estradiol and higher. Pre- and postimplantation losses were significantly increased when 10 mg/kg/day drospirenone + 0.1 mg/kg/day ethinyl estradiol were administered during the preimplantation phase of gestation in rats.
No teratogenicity was observed following intragastric administration of drospirenone, alone or in combination with ethinyl estradiol, to female rats, rabbits, and/or monkeys, prior to mating or during gestation. Compound-related maternal toxicity, characterized by decreased body weight gain (rats) and occasional vomiting (monkeys), was observed. The incidence of abortions was increased following administration of high doses of drospirenone (100 mg/kg/day) to pregnant rabbits, and a dose-dependent increase in abortions occurred following the administration of all doses to monkeys. Embryotoxicity and slight retardations of fetal development (e.g., delayed ossification of feet bones, sternebrae, vertebrae; incomplete ossification of skull; slight increase in visceral abnormalities) were observed in the rat and rabbit at drospirenone doses of 15 mg/kg/day and 100 mg/kg/day, respectively.
Virilization of female fetuses (attributed to ethinyl estradiol) and feminization of male fetuses (attributed to drospirenone) were observed following administration of the drug combination to pregnant rats on Days 14 through 21 of pregnancy, beginning at doses of 5+0.05 mg/kg and 15+0.15 mg/kg, respectively. If exposure estimates from nonpregnant rats are extrapolated to pregnant animals, the administration of 15 mg/kg/day drospirenone would result in plasma exposure levels which are at least 10 times higher than the steady-state human exposure after intake of YASMIN.
Prolonged or incomplete parturition or inability to deliver was observed when the drug combination was administered to rats from Day 15 of gestation through Day 3 postpartum. In the rat peri-/postnatal study, treatment from Days 15-18 of gestation and Days 1-22 postpartum caused a dose-dependent delay in postnatal development (body weight, physical and functional parameters) and a dose-dependent increased mortality of the F1 offspring. These observations were attributed to the negative effects of drospirenone and/or ethinyl estradiol on lactogenesis and milk secretion.
A reduced reproductive performance of the F1 animals was observed at the dose of 45 mg/kg/day drospirenone + 0.45 mg/kg/day ethinyl estradiol. This was attributed to an impairment of sex organ development in the male offspring due to the antiandrogenic activity of drospirenone.