


Product Monograph - Zoledronic Acid Injection (Juno Pharma Canada)
SUMMARY PRODUCT INFORMATION
| Route of Administration | Dosage Form / Strength | Non-medicinal Ingredients |
|---|---|---|
| Intravenous infusion | Solution, 5 mg / 100 mLª |
|
ª One bag with 100 mL solution contains 5.330 mg of zoledronic acid monohydrate, equivalent to 5 mg zoledronic acid on an anhydrous basis.
INDICATIONS AND CLINICAL USE
Zoledronic Acid Injection (zoledronic acid 5 mg / 100 mL) is indicated for:
- The treatment of osteoporosis in postmenopausal women, as a once-yearly intravenous infusion, to reduce the incidence of hip, vertebral and non-vertebral fractures.
- The treatment to increase bone mineral density in men with osteoporosis, as a once-yearly intravenous infusion.
- The treatment and prevention of glucocorticoid-induced osteoporosis, to increase bone mineral density, as a once-yearly intravenous infusion.
- The prevention of postmenopausal osteoporosis in women with osteopenia as a single intravenous infusion.
- The treatment of Paget’s disease of the bone in men and women, as a single-dose intravenous infusion. Treatment is indicated in patients with Paget’s disease of the bone with elevations in serum alkaline phosphatase (SAP) of at least two times the upper limit of the age-specific normal reference range, or those who are symptomatic, or those at risk for complications from their disease to induce remission (normalization of serum alkaline phosphatase). The effectiveness of zoledronic acid injection is based on serum alkaline phosphatase (SAP) levels.
Geriatrics (> 65 years of age):
No overall differences in safety and efficacy were observed according to age (see WARNINGS AND PRECAUTIONS, Special Populations).
Pediatrics (<18 years of age):
Safety and efficacy in children and growing adolescents have not been established. Zoledronic Acid Injection should not be given to this patient population.
Important Limitations of Use:
The optimal duration of use has not been determined. Patients should have the need for continued therapy re-evaluated on a periodic basis (see DOSAGE AND ADMINISTRATION).
CONTRAINDICATIONS
- Patients who are hypersensitive to this drug or to any ingredient in the formulation, or to any bisphosphonates or component of the container. For a complete listing, see the Dosage Forms, Composition and Packaging section of the Product Monograph.
- Severe renal impairment with creatinine clearance <35 mL/min and in those with evidence of acute renal impairment. These patients are at an increased risk of renal failure (see WARNINGS and PRECAUTIONS).
- Pregnancy and nursing mothers.
- Non-corrected hypocalcaemia at the time of infusion.
WARNINGS AND PRECAUTIONS
General
Zoledronic Acid Injection contains the same active ingredient that is found in ZOMETA® (zoledronic acid). Patients being treated with ZOMETA® (zoledronic acid) should not be treated with Zoledronic Acid Injection.
Patients being treated with Zoledronic Acid Injection should not be treated with other bisphosphonates concomitantly.
Patients must be appropriately hydrated prior to administration of Zoledronic Acid Injection, especially for patients who are elderly or on diuretic therapy.
Infusion duration
The 5 mg single dose of Zoledronic Acid Injection 5 mg / 100 mL should be infused in no less than 15 minutes.
Cardiovascular
Atrial fibrillation
There have been reports of serious atrial fibrillation in patients treated with zoledronic acid. Atrial fibrillation may occur at any time during treatment.
Overall incidence of atrial fibrillation in the 3-year postmenopausal osteoporosis trial (HORIZON-PFT) using zoledronic acid 5 mg dose yearly, was 2.5% (96 out of 3,862) and 1.9% (75 out of 3,852) in patients receiving zoledronic acid and placebo, respectively. The rate of atrial fibrillation serious adverse events was 1.3% (51 out of 3,862) and 0.6% (22 out of 3,852) in patients receiving zoledronic acid and placebo, respectively. The overall incidence of atrial fibrillation in the 2-year male osteoporosis trial was 3.3 % (5 out of 153) for zoledronic acid-treated patients compared to 2% (3 out of 148) for alendronate-treated patients. The rate of atrial fibrillation serious adverse events was 0% for zoledronic acid-treated patients compared to 0.7% (1/148) for alendronate-treated patients. The overall incidence of atrial fibrillation in the 1-year glucocorticoid induced-osteoporosis trial was 0.7 % (3 out of 416) for zoledronic acid-treated patients compared to 0.0% (0 out of 417) for risedronate-treated patients. The rate of atrial fibrillation serious adverse events was 0% for zoledronic acid-treated patients and 0% for risedronate-treated patients. This increased incidence of atrial fibrillation was not observed in clinical trials conducted in Paget’s disease, in the HORIZON-RFT trial in post-hip fracture patients, or in the trial for the prevention of postmenopausal osteoporosis. The mechanism behind the increased incidence of atrial fibrillation is unknown.
Cerebrovascular Accident
There have been reports of serious cerebrovascular accidents in patients treated with zoledronic acid, some with a fatal outcome.
The signs and symptoms of cerebrovascular accidents can occur at any time during treatment.
Endocrine and Metabolism
Hypocalcemia
It is recommended that all patients should have their serum calcium levels and vitamin D levels assessed before treatment with Zoledronic Acid Injection (e.g., as part of their annual examination). Pre- existing hypocalcemia must be treated by adequate administration of calcium and vitamin D before initiating Zoledronic Acid Injection (see CONTRAINDICATIONS). Other disturbances of mineral metabolism (e.g., diminished parathyroid reserve; thyroid surgery, parathyroid surgery, intestinal calcium malabsorption) must also be effectively treated.
It is strongly advised that patients receive adequate calcium and vitamin D supplementation. All patients should be counseled regarding the importance of calcium and vitamin D supplementation in maintaining serum calcium levels and on the symptoms of hypocalcemia. The recommended daily vitamin D supplement should be determined by the treating physician based on the patient's individual needs. In the postmenopausal osteoporosis trial (HORIZON- PFT), patients received 1000 to 1500 mg of elemental calcium plus 400 to 1200 IU of vitamin D supplements per day.
Renal
The use of Zoledronic Acid Injection in patients with severe renal impairment (creatinine clearance <35 mL/min) and in those with evidence of acute renal impairment is contraindicated due to an increased risk of renal failure in this population (see DOSAGE AND ADMINISTRATION). Zoledronic acid has been associated with renal dysfunction manifested as deterioration in renal function, and acute renal failure (see ADVERSE REACTIONS, Clinical Trial Adverse Drug Reactions and Post-Market Adverse Drug Reactions). Renal impairment has been observed following the administration of zoledronic acid injection, including after a single administration. Renal failure requiring dialysis or with a fatal outcome has occurred especially in patients with history of renal impairment or other risk factors. Risk factors include advanced age, concomitant nephrotoxic medicinal products, concomitant diuretic therapy (see DRUG INTERACTIONS), or dehydration occurring after zoledronic acid injection administration. It may increase with underlying renal disease and dehydration secondary to fever, sepsis, gastrointestinal losses, diuretic therapy, advanced age, etc. (see Post-Market Adverse Drug Reactions). In some post marketing cases, acute renal failure has occurred in patients with no underlying risk factors for renal impairment. Renal impairment may lead to increased exposure of concomitant medications and/or their metabolites that are primarily renally excreted (see DRUG INTERACTIONS).
The following precautions should be taken to minimize the risk of renal adverse reactions:
- Creatinine clearance should be calculated based on actual body weight using Cockcroft-Gault formula before each Zoledronic Acid Injection dose. Transient increase in serum creatinine may be greater in patients with underlying impaired renal function. Interim monitoring of creatinine clearance should be performed in at-risk patients.
- Zoledronic Acid Injection should be used with caution when concomitantly used with other medicinal products that could impact renal function (see DRUG INTERACTIONS). Creatinine clearance should be monitored in patients at-risk for acute renal failure who are taking concomitant medications that are primarily excreted by the kidney
- Patients should be appropriately hydrated, prior to administration of Zoledronic Acid Injection, especially elderly patients and those receiving diuretic therapy. On the day of infusion, it is recommended that patients eat and drink normally, which includes drinking at least 2 glasses of fluids (500 mL or 2 cups), such as water, before and after the administration of Zoledronic Acid Injection (see Information to be provided to the Patients).
- A single dose of Zoledronic Acid Injection should not exceed 5 mg and the duration of infusion should not be less than 15 minutes (see DOSAGE AND ADMINISTRATION).
Musculoskeletal
Osteonecrosis of the Jaw
Osteonecrosis of the jaw (ONJ) has been reported in the treatment of osteoporosis with zoledronic acid as well as with other oral and intravenous bisphosphonates including in, but not limited to, patients with cancer receiving treatment or patients that underwent invasive dental procedures, such as root canal or dental extraction (see ADVERSE REACTIONS, Post- Market Adverse Drug Reactions).
Prior to each treatment with Zoledronic Acid Injection, a routine oral examination should be performed. Patients with possible risk factors (e.g., cancer, chemotherapy, angiogenesis inhibitors, head and neck radiotherapy, corticosteroids, poor oral hygiene, diabetes) should be referred to a dentist for examination and appropriate preventive dentistry should be performed prior to treatment with Zoledronic Acid Injection.
During the treatment with zoledronic acid, patients should maintain good oral hygiene, undergo routine dental check-ups, and immediately report any oral symptoms. While receiving treatment, these patients should avoid invasive dental procedures, if possible, but should continue with regular dental cleaning and oral hygiene. For patients requiring oral surgery, there are no data available to suggest whether discontinuation of bisphosphonate treatment reduces the risk of ONJ. In patients who develop ONJ while on bisphosphonate therapy, surgery at the affected area may exacerbate the condition. Clinical judgment of the treating physician should guide the management plan of each patient based on individual benefit/risk assessment.
The start of treatment, or of a new course of treatment, should be delayed in patients with unhealed open soft tissue lesions in the mouth.
The following should be considered when evaluating a patient’s risk of developing ONJ:
- Potency of the medicinal product that inhibits bone resorption (higher risk for highly potent compounds)
- Route of administration (higher risk for parenteral administration)
- Cumulative dose of bone resorption therapy
- Co-morbid conditions (e.g. anemia, coagulopathies) and smoking
- Periodontal disease, poorly fitting dentures, history of dental disease.
Temporary interruption of Zoledronic Acid Injection treatment should be considered until the conditions resolves and contributing factors are mitigated where possible.
Osteonecrosis of other bones
Post-market reports of osteonecrosis of other bones, including femur, hip, knee and humerus, have been reported with zoledronic acid injection. Spontaneous reports of osteonecrosis of the external auditory canal have been reported with zoledronic acid and other bisphosphanates (see ADVERSE REACTIONS, Post-Market Adverse Drug Reactions).
Atypical Subtrochanteric and Diaphyseal Femoral Fractures
Atypical, low-energy, or low trauma fractures of the femoral shaft have been reported in bisphosphonate-treated patients. These fractures can occur anywhere in the femoral shaft from just below the lesser trochanter to above the supracondylar flare and are transverse or short oblique in orientation without evidence of comminution. Atypical femur fractures most commonly occur with minimal or no trauma to the affected area. They may be bilateral and many patients report prodromal pain in the affected area, usually presenting as dull, aching thigh pain, weeks to months before a complete fracture occurs. Poor healing of these fractures was also reported. Any patient with a history of bisphosphonate exposure who presents with thigh or groin pain should be suspected of having an atypical fracture and should be evaluated to rule out an incomplete femur fracture. Patients presenting with an atypical femur fracture should also be assessed for symptoms and signs of fracture in the contralateral limb. Interruption of bisphosphonate therapy should be considered pending a risk/benefit assessment. Although causality has not been established, the role of bisphosphonates cannot be ruled out.
Musculoskeletal Pain
In post-marketing experience with multiple dose regimen bisphosphonates, including zoledronic acid injection, severe and occasionally incapacitating bone, joint, and/or muscle pain has been reported in patients. The time to onset of symptoms varied from one day to several months after starting the drug. A subset of patients had recurrence of symptoms when rechallenged with the same drug or another bisphosphonate.
Respiratory
While not observed in clinical trials with zoledronic acid injection, there have been reports of bronchoconstriction in ASA (acetylsalicylic acid) sensitive patients receiving bisphosphonates. Zoledronic Acid Injection must be used with caution in ASA-sensitive patients.
Ophthalmologic
Ocular disturbances including conjunctivitis, uveitis, episcleristis, iritis, scleritis and orbital inflammation have been reported with zoledronic acid injection therapy. Patients with ocular events other than uncomplicated conjunctivitis should be referred to an ophthamologist for evaluations. Treatment may need to be discontinued.
Sexual Function/Reproduction
Fertility
Fertility was decreased in female rats dosed subcutaneously with 0.1 mg/kg/day of zoledronic acid. There are no data available in humans.
Special Populations
Pregnant Women
Zoledronic Acid Injection is contraindicated (see CONTRAINDICATIONS) during pregnancy as zoledronic acid may cause fetal harm when administered to a pregnant woman. In reproductive studies in the pregnant rat, subcutaneous doses equivalent to 2.0 or 4.5 times the human systemic exposure (an i.v. dose of 5 mg based on an AUC comparison) resulted in pre- and post-implantation losses, decreases in viable fetuses and fetal skeletal, visceral and external malformations. The impact of variables such as time between cessation of bisphosphonate therapy to conception, the particular bisphosphonate used, and the route of administration on this risk have not been established.
There are no studies in pregnant women using zoledronic acid. If the patient becomes pregnant while taking this drug, the patient should be apprised of the potential harm to the fetus. Women of childbearing potential should be advised to avoid becoming pregnant.
Nursing Women
It is not known whether zoledronic acid is excreted in human milk. Because many drugs are excreted in human milk, it should not be administered to a nursing woman.
Pediatrics (<18 years of age)
The safety and effectiveness of zoledronic acid injection in pediatric patients have not been established.
Geriatrics (>65 years of age)
The combined osteoporosis trials (HORIZON-PFT and HORIZON-RFT) included 4,761 zoledronic acid injection-treated patients who were at least 65 years of age, while 2,083 patients were at least 75 years old. No overall differences in safety and efficacy were observed according to age.
The osteoporosis study in men included 59 (38.3%) zoledronic acid injection-treated patients who were at least 65 years of age, while 24 (15.6%) patients were at least 75 years old. No overall differences in safety and efficacy were observed according to age.
The glucocorticoid-induced osteoporosis trial included 116 (27.9%) zoledronic acid injection-treated patients who were at least 65 years of age, while 29 (7.0%) patients were at least 75 years old. No overall differences in safety and efficacy were observed according to age.
Phase 3 studies of zoledronic acid injection in the treatment of Paget’s disease of bone included 132 (75.5%) zoledronic acid injection-treated patients who were at least 65 years of age, while 68 (37.4%) zoledronic acid injection-treated patients were at least 75 years old. No overall differences in efficacy or safety were observed between these patients and younger patients.
Information to be Provided to the Patient
Physicians should instruct their patients to read the Patient Information before starting therapy with Zoledronic Acid Injection.
- Zoledronic Acid Injection is given as one single infusion into a vein by a nurse or a doctor, and the infusion time must not be less than 15 minutes.
- Before being given Zoledronic Acid Injection, patients should tell their doctor if they have kidney problems and what medications they are taking (see ADVERSE REACTIONS, Renal impairment).
- Zoledronic Acid Injection should not be given if the patient is taking ZOMETA (zoledronic acid), which contains the same active ingredient as in Zoledronic Acid Injection.
- Zoledronic Acid Injection should not be given if the patient is pregnant or plans to become pregnant, or if they are breast-feeding (see CONTRAINDICATIONS and WARNINGS AND PRECAUTIONS).
- If the patient had surgery to remove some or all of the parathyroid glands or thyroid gland in their neck, or had sections of their intestine removed, or are unable to take calcium supplements, they should tell the doctor.
- It is strongly advised that patients receive adequate calcium and vitamin D supplementation in order to maintain normal blood calcium levels. Supplementation of both calcium and vitamin D is especially important in the days before and following Zoledronic Acid Injection administration. The recommended daily vitamin D supplement should be determined by the treating physician based on the patient's individual needs.
- On the day of infusion, it is recommended that patients eat and drink normally, which includes drinking at least 2 glasses of fluids (500 mL or 2 cups) such as water, before and after the administration of Zoledronic Acid Injection.
- Patients should also be aware of the most common side effects. Patients may experience one or more side effects that could include: fever and chills; muscle, bone or joint pain; nausea; fatigue; and headache. Most of these side effects are mild to moderate and occur within 3 days after taking Zoledronic Acid Injection. They usually go away within 3 days after they start, but may last for up to 7-14 days. The incidence of post-dose symptoms occurring within the first 3 days after administration of Zoledronic Acid Injection, can be reduced with the administration of acetaminophen or ibuprofen shortly following Zoledronic Acid Injection administration.
- Some patients experienced hypocalcemia. Hypocalcemia is usually asymptomatic, but symptoms may include numbness or tingling sensations, especially in the area around the mouth, muscle cramps or muscle spasms. Patients should consult their physician immediately if they develop these symptoms of hypocalcemia after Zoledronic Acid Injection treatment (see ADVERSE REACTIONS).
- Redness, swelling and or pain at the infusion site may occur. Redness, itching, or pain to the eyes may occur.
- There have been some reports of persistent pain and/or a non-healing sore of the mouth or jaw. Patients should tell their doctor or dentist if they experience these symptoms.
- There have been some reports of eye inflammation. Patients should consult their physician if this occurs.
Monitoring and Laboratory Tests
Hypocalcemia: Serum calcium levels and vitamin D levels should be assessed for all patients before treatment with Zoledronic Acid Injection (e.g., as part of their annual examination). The recommended daily vitamin D supplement should be determined by the treating physician based on the patient's individual needs.
Renal: Creatinine clearance should be calculated before each dose of Zoledronic Acid Injection. Interim monitoring of creatinine clearance should be performed in at-risk patients.
Osteonecrosis of the Jaw: Prior to each treatment with Zoledronic Acid Injection, a routine oral examination should be performed. Patients with possible risk factors (e.g., cancer, chemotherapy, angiogenesis inhibitors, head and neck radiotherapy, corticosteroids, poor oral hygiene, diabetes) should be referred to a dentist for examination and appropriate preventive dentistry should be performed prior to treatment with Zoledronic Acid Injection. Patients should receive routine dental check-ups while taking Zoledronic Acid Injection.
ADVERSE REACTIONS
Adverse Drug Reaction Overview
- Postmenopausal osteoporosis
In the postmenopausal osteoporosis trial (HORIZON-PFT), Phase III randomized, double-blind, placebo-controlled, multinational study of 7,736 women aged 65-89 years (see CLINICAL TRIALS), there were no significant differences in the overall incidence of serious adverse events compared to placebo and most adverse events were mild to moderate. The duration of the trial was three years with 3,862 patients exposed to zoledronic acid injection and 3,852 patients exposed to placebo administered once annually as a single 5 mg dose in 100 mL solution infused over at least 15 minutes, for a total of three doses. All women received 1000 to 1500 mg of elemental calcium plus 400 to 1200 IU of vitamin D supplementation per day.
The incidence of all-cause mortality was: 3.4% in the zoledronic acid injection group and 2.9% in the placebo group. The incidence of serious adverse events was similar between treatment groups 29.2% in the zoledronic acid injection group and 30.1% in the placebo group. The percentage of patients who withdrew from the study due to adverse events was 2.1% and 1.8% for the zoledronic acid injection and placebo groups, respectively. The rate of atrial fibrillation serious adverse events was 1.3% (51 out of 3,862) and 0.6% (22 out of 3,852) in patients receiving zoledronic acid injection and placebo, respectively.
Zoledronic acid injection has been most commonly associated with the following post-dose symptoms: fever (18.1%), myalgia (9.4%), flu-like symptoms (7.8%), arthralgia (6.8%) and headache (6.5%), the majority of which occur within the first 3 days following zoledronic acid injection administration. The majority of these symptoms were mild to moderate in nature and resolved within 3 days of the event onset. The incidence of these symptoms decreased markedly with subsequent doses of zoledronic acid injection.
The incidence of post-dose symptoms occurring within the first 3 days after administration of Zoledronic Acid Injection, can be reduced with the administration of acetaminophen or ibuprofen shortly following Zoledronic Acid Injection administration as needed.
In the HORIZON-RFT trial (see CLINICAL TRIALS), a randomized, double-blind, placebo- controlled, multinational endpoint study of 2,127 osteoporotic patients aged 50-95 years with a recent (within 90 days) low-trauma hip fracture, 1,054 patients were exposed to zoledronic acid injection and 1,057 patients were exposed to placebo. Zoledronic acid injection was administered once annually as a single 5 mg dose in 100 mL solution infused over at least 15 minutes. All participants received 1000 to 1500 mg of elemental calcium plus 800 to 1200 IU of vitamin D supplementation per day.
The incidence of all-cause mortality was 9.6% in the zoledronic acid injection-treated group compared to 13.3% in the placebo group. The incidence of serious adverse events was 38% in the zoledronic acid injection group and 41% in the placebo group. The percentage of patients who withdrew from the study due to adverse events was 2.0% and 1.7% for the zoledronic acid injection and placebo groups, respectively.
- Osteoporosis in men
In general, zoledronic acid injection was well tolerated in the male osteoporosis trial as assessed in a two-year randomized, multicentre, double-blind, active-controlled group study of 302 men aged 25-86 years. 153 patients were exposed to zoledronic acid injection administered once annually as a single 5 mg dose in 100 mL solution infused over 15 minutes for a total of two doses and 148 patients were exposed to oral alendronate 70 mg weekly for two years. All participants received 1000 mg elemental calcium plus 800 to 1000 IU vitamin D supplementation per day (see CLINICAL TRIALS).
The incidence of serious adverse events was similar between the zoledronic acid injection and alendronate treatment groups (17.6% vs. 20.9%, respectively). The percentage of patients who withdrew from the study due to serious adverse events was 4.6% and 3.4% for the zoledronic acid injection and alendronate groups, respectively. The percentage of patients experiencing at least one adverse event was comparable between the zoledronic acid injection and alendronate treatment groups (93.5% compared to 93.2%), with the exception of a higher incidence of post-dose symptoms in the zoledronic acid injection group that occurred within 3 days after infusion. The incidence of these post-dose symptoms were reported as follows for zoledronic acid injection and alendronate, respectively: myalgia (17.1% vs. 2.7%), fever (15.7% vs. 1.4%), fatigue (12.4% vs. 1.4%), arthralgia (11.1% vs. 0.7%), pain (10.5% vs. 2.7%), chills (9.8% vs. 0.7%), headache (9.8% vs. 2.0%), influenza-like illness (8.5% vs. 2.0%), malaise (5.2% vs. 0.7%), and back pain (3.3% vs. 0.7%).
- Glucocorticoid-induced osteoporosis
In general, zoledronic acid injection was well tolerated in the glucocorticoid-induced osteoporosis trial (see CLINICAL TRIALS).
The duration of the trial was one year, with 416 patients exposed to zoledronic acid injection administered once as a single infusion 5 mg dose in 100 mL solution infused over 15 minutes and 417 patients exposed to oral risedronate 5 mg daily for one year. All participants received 1000 mg elemental calcium plus 400 to 1000 IU vitamin D supplementation per day.
The overall percentage of adverse events was higher for the zoledronic acid group compared to the risedronate group (77.4% vs. 66.9%, respectively) driven by a higher incidence of post-dose symptoms in the zoledronic acid injection group that occurred within 3 days after infusion. The most common post-dose symptoms were reported as follows for zoledronic acid injection and risedronate, respectively: pyrexia (12.7% vs. 3.6%), arthralgia (9.9% vs. 7.4%), nausea (9.6% vs. 8.4%), myalgia (9.1% vs. 3.4%), and influenza-like illness (6% vs. 1%).
The incidence of serious adverse events was similar between the zoledronic acid injection and risedronate treatment groups (14.7% vs. 14.4%, respectively). The percentage of patients who withdrew from the study due to adverse events was 7.9% for the zoledronic acid injection group and 5.3% for the risedronate group.
- Prevention of postmenopausal osteoporosis
The safety of zoledronic acid injection in postmenopausal women with osteopenia (low bone mass) was assessed in a 2-year randomized, double-blind, placebo-controlled trial of postmenopausal women aged 45 years or older. 181 women were exposed to zoledronic acid injection as a single 5 mg dose administered at randomisation and 202 patients were exposed to placebo for two years (see CLINICAL TRIALS). All women received 500 to 1200 mg elemental calcium plus 400 to 800 IU vitamin D supplementation per day.
The incidence of serious adverse events was 9.4% and 11.4% for the zoledronic acid and the placebo groups, respectively. The percentage of patients who withdrew from the study due to adverse events was 1.7% and 0.5% for the zoledronic acid and the placebo groups, respectively.
The incidence of the most frequent treatment-emergent adverse events for the zoledronic acid group was reported as follows: myalgia (22.7%), pyrexia (21%), headache (20.4%), chills (18.2%), pain in extremity (16%), pain (14.9%), nausea (11.6%), fatigue (9.9%), influenza (8.3%), non-cardiac chest pain (7.7%), dizziness (6.1%), hypercholesterolemia (5.5%), sciatica (5%), bone pain (3.3%), asthenia (2.8%), and hypoesthesia (2.2%).
- Paget’s disease of bone
In general, zoledronic acid injection was well-tolerated in Paget’s disease trials. Consistent with intravenous administration of bisphosphonates, zoledronic acid injection has been most commonly associated with the following signs and symptoms, the majority of which occur within 3 days following the administration: influenza-like illness (transient post-dose symptoms), pyrexia, myalgia, arthralgia, and bone pain. In Paget’s disease trials, one or more of these events which were suspected to be related to drug were reported in 25% of patients in the zoledronic acid injection-treated group compared to 8% in the risedronate-treated group within the first 3 days following the zoledronic acid injection administration. After the first 3 days, rates for these symptoms were reduced to 3% for zoledronic acid injection-treated patients and 3% for risedronate-treated patients. The majority of these symptoms resolved within 3 days of their onset.
Clinical Trial Adverse Drug Reactions
Because clinical trials are conducted under very specific conditions the adverse reaction rates observed in the clinical trials may not reflect the rates observed in practice and should not be compared to the rates in the clinical trials of another drug. Adverse drug reaction information from clinical trials is useful for identifying drug-related adverse events and for approximating rates.
- Postmenopausal osteoporosis
Adverse reactions reported in at least 2.0% of the postmenopausal osteoporosis patients, and more frequently in the zoledronic acid injection-treated patients than placebo-treated patients are shown in Table 1.
Table 1. Adverse Reactions Occurring in ≥ 2.0% of Postmenopausal Osteoporosis Patients Receiving zoledronic acid injection (5 mg IV Infusion Once Yearly) and More Frequently than in Placebo - Treated Patients Over 3 Years
System Organ Class
5 mg IV
zoledronic acid injection
Placebo once per year
once per year
%
%
(N=3862)
(N=3852)
Blood and the Lymphatic System Disorders
Anaemia
4.4
3.6
Metabolism and Nutrition Disorders
Anorexia
2.0
1.1
Nervous System Disorders
Headache
12.4
8.1
Dizziness
7.6
6.7
System Organ Class
5 mg IV
zoledronic acid injection
Placebo once per year
once per year
%
%
(N=3862)
(N=3852)
Vascular Disorders
Hypertension
12.7
12.4
Ear and Labyrinth Disorders
Vertigo
4.3
4.0
Cardiac Disorders
Atrial Fibrillation
2.4
1.9
Gastrointestinal Disorders
Nausea
8.5
5.2
Diarrhea
6.0
5.6
Vomiting
4.6
3.2
Abdominal Pain Upper
4.6
3.1
Dyspepsia
4.3
4.0
Musculoskeletal, Connective Tissue and Bone Disorders
Arthralgia
23.8
20.4
Myalgia
11.7
3.7
Pain in Extremity
11.3
9.9
Shoulder Pain
6.9
5.6
Bone Pain
5.8
2.3
Neck Pain
4.4
3.8
Muscle Spasms
3.7
3.4
General Disorders and Administrative Site Conditions
Pyrexia
17.9
4.6
Influenza-like Illness
8.8
2.7
Fatigue
5.4
3.5
Chills
5.4
1.0
Asthenia
5.3
2.9
Peripheral Edema
4.6
4.2
Pain
3.3
1.3
Malaise
2.0
1.0
The incidence of post-dose symptoms decreased after each annual infusion. Table 2 presents the overall incidence of adverse events by time of onset from infusion by first, second and third infusion.
Table 2: Overall incidence of adverse events in the postmenopausal osteoporosis trial by infusion and time of onset (Safety population)
| Infusion | 1st infusion | 2nd infusion | 3rd infusion | |||||||||||||||
Zoledronic acid injection n (%) | Placebo n (%) | Zoledronic acid injection n (%) | Placebo n (%) | Zoledronic acid injection n (%) | Placebo n (%) | |||||||||||||
| Total no. of patients with infusion | 3862 | 3852 | 3409 | 3517 | 3106 | 3190 | ||||||||||||
Time of onset ≤ 3 days | 1726 (44.69) | 571 (14.82) | 570 (16.72) | 462 (10.29) | 316 (10.17) | 270 (8.46) | ||||||||||||
Table 3: Adverse reactions occurring in at least 2% of men and women with a low trauma hip fracture receiving zoledronic acid injection (5 mg IV Infusion once yearly) and greater than placebo
| System Organ Class | 5 mg IV zoledronic acid injection once per year % (N=1054) | Placebo | |||
| once per year | |||||
| % | |||||
| (N=1057) | |||||
| Nervous System Disorders | |||||
| Headache | 3.8 | 2.5 | |||
Vascular disorders Hypertension | 6.8 | 5.4 | |||
Musculoskeletal, Connective Tissue and Bone Disorders Pain in extremity | 5.9 | 4.8 | |||
| Myalgia | 4.9 | 2.6 | |||
| Bone pain | 3.2 | 1.0 | |||
| Musculoskeletal pain | 3.1 | 1.2 | |||
General Disorders and Administrative Site Conditions Pyrexia | 8.7 | 3.1 | |||
| Edema peripheral | 5.5 | 5.3 | |||
| Hyperthermia | 2.2 | 0.3 | |||
| Fatigue | 2.1 | 1.2 | |||
| Injury, poisoning, and procedural complications | |||||
| Post procedure complication | 3.8 | 3.3 | |||
| Osteoarthritis | 5.7 | 4.5 | |||
| Cataracts | 3.0 | 2.3 | |||
| Urinary tract infection | 10.6 | 9.6 | |||
- Osteoporosis in men
The overall safety and tolerability profile of zoledronic acid injection in male osteoporosis was similar to that reported in the zoledronic acid injection postmenopausal osteoporosis trial (HORIZON-PFT). Adverse events reported in at least 2% of men with osteoporosis that were either not reported in the postmenopausal osteoporosis trial (HORIZON-PFT) or reported more frequently in the osteoporosis trial in men are presented in Table 4.
Table 4: Adverse reactions occurring in ≥ 2%+ of patients with male osteoporosis receiving zoledronic acid injection (5-mg IV Infusion once yearly) or 70 mg once weekly of alendronate over 24 months
| 5 mg IV zoledronic acid injection | Alendronate 70 mg/ | |||||||||
| System Organ Class | once per year | once weekly | ||||||||
| % | % | |||||||||
| (N=153) | (N=148) | |||||||||
| Nervous System Disorders | ||||||||||
| Headache | 15.0 | 6.1 | ||||||||
| Lethargy | 3.3 | 1.4 | ||||||||
Eye Disorders Eye pain | 2.0 | 0.0 | ||||||||
| Cardiac disorders | ||||||||||
| Atrial fibrillation | 3.3 | 2.0 | ||||||||
| Palpitations | 2.6 | 0.0 | ||||||||
Gastrointestinal disorder Abdominal pain∆ | 7.9 | 4.1 | ||||||||
Respiratory, thoracic and mediastinal disorders Dyspnea | 6.5 | 4.7 | ||||||||
| Skin and subcutaneous tissue disorders | ||||||||||
| Hyperhidrosis | 2.6 | 2.0 | ||||||||
| Rash | 2.0 | 2.7 | ||||||||
| Musculoskeletal, Connective Tissue and Bone Disorders | ||||||||||
| Myalgia | 19.6 | 6.8 | ||||||||
| Musculoskeletal pain**® | 12.4 | 10.8 | ||||||||
| Musculoskeletal stiffness | 4.6 | 0.0 | ||||||||
| Back pain | 12.4 | 17.6 | ||||||||
| Renal and urinary disorders | ||||||||||
| Blood creatinine increased | 2.0 | 0.7 | ||||||||
| General Disorders and Administrative Site Conditions | ||||||||||
| Fatigue | 17.6 | 6.1 | ||||||||
| Pain | 11.8 | 4.1 | ||||||||
| Chills | 9.8 | 2.7 | ||||||||
| Influenza like illness | 9.2 | 2.0 | ||||||||
| Malaise | 7.2 | 0.7 | ||||||||
| Acute phase reaction | 3.9 | 0.0 | ||||||||
Investigations C-reactive protein increased | 4.6 | 1.4 | ||||||||
+ includes adverse reactions that occurred in ≥2% of patients which were either not reported in the postmenopausal osteoporosis trial or reported more frequently in the trial of men with osteoporosis
∆ Combined abdominal pain, abdominal pain upper, and abdominal pain lower as one ADR
** Combined musculoskeletal pain and musculoskeletal chest pain as one ADR
- Glucocorticoid-induced osteoporosis
The overall safety and tolerability profile of zoledronic acid injection in the glucocorticoid-induced osteoporosis trial was similar to that reported in the zoledronic acid injection postmenopausal osteoporosis clinical trial (HORIZON-PFT). Adverse events reported in at least 2% of patients that were either not reported in the postmenopausal osteoporosis trial (HORIZON-PFT) or reported more frequently in the glucocorticoid-induced osteoporosis trial included the following: abdominal pain+ (zoledronic acid injection 7.5%; risedronate 5.0%), and musculoskeletal pain++ (zoledronic acid injection 3.1%; risedronate 1.7%). In addition, the following adverse events occurred more frequently than in the postmenopausal osteoporosis trial: nausea (zoledronic acid injection 9.6%; risedronate 8.4%), rheumatoid arthritis (zoledronic acid injection 6.3%; risedronate 5%), dyspepsia (zoledronic acid injection 5.5%; risedronate 4.3%), urinary tract infection (zoledronic acid injection 5%; risedronate 4.1%) and back pain (zoledronic acid injection 4.3%; risedronate 6.2%).
+ Combined abdominal pain, abdominal pain upper, and abdominal pain lower as one ADR
++ Combined musculoskeletal pain and musculoskeletal chest pain as one ADR
In the one-year glucocorticoid-induced osteoporosis trial, arrhythmia and tachycardia were reported in 1% (4 out of 416) of zoledronic acid-treated patients compared to 0.0% arrhythmia and 0.5% (2 out of 417) tachycardia in the risedronate-treated patients.
- Prevention of postmenopausal osteoporosis
Table 5: Adverse reactions occurring in at least 2% of women with osteopenia receiving zoledronic acid injection 5 mg IV infusion (administered as a single dose at randomisation) and greater than placebo in the prevention of postmenopausal osteoporosis trial over 2 years
| System Organ Class | Zoledronic acid injection 5 mg IV % | Placebo % |
| System Organ Class | Zoledronic acid injection 5 mg IV % | Placebo % |
| (N=181) | (N=202) | |
| (N=181) | (N=202) | |
Endocrine Disorders Hypothyroidism | 2.8 | 1.5 |
| Gastrointestinal disorders | ||
| Nausea | 11.6 | 7.9 |
| Constipation | 7.2 | 6.9 |
| Dyspepsia | 6.6 | 5.0 |
| Vomiting | 5.0 | 4.5 |
Vascular disorders Hypertension | 8.3 | 6.9 |
| Musculoskeletal, Connective Tissue and Bone Disorders | ||
| Myalgia | 22.7 | 6.9 |
| Back pain | 16.6 | 11.9 |
| Pain in extremity | 16.0 | 9.9 |
| Neck pain | 6.6 | 5.0 |
| Musculoskeletal pain | 5.5 | 5.4 |
| Pain in jaw | 3.9 | 2.5 |
| Bone pain | 3.3 | 1.0 |
| Arthritis | 2.2 | 1.5 |
General Disorders and Administrative Site Conditions Pyrexia | 21.0 | 4.5 |
| Chills | 18.2 | 3.0 |
| Pain | 14.9 | 3.5 |
| Fatigue | 9.9 | 4.0 |
| Non-cardiac chest pain | 7.7 | 3.0 |
| Edema peripheral | 3.9 | 3.5 |
| Influenza-like illness | 3.3 | 2.0 |
| Asthenia | 2.8 | 1.0 |
| Malaise | 2.2 | 0.5 |
| Immune system disorders | ||
| Seasonal allergy | 2.8 | 1.5 |
Infections and infestations Influenza | 8.3 | 5.9 |
| Tooth infection | 2.8 | 1.0 |
| Injury, poisoning, and procedural complications | ||
| Joint sprain | 2.8 | 1.5 |
| Post-traumatic pain | 2.8 | 2.5 |
Metabolism and nutrition disorders Hypercholesterolemia | 5.5 | 2.0 |
| Nervous system disorders | ||
| Headache | 20.4 | 11.4 |
| Dizziness | 6.1 | 3.5 |
| Sciatica | 5.0 | 2.0 |
| Hypoaesthesia | 2.2 | 2.0 |
Reproductive system and breast disorders Vulvovaginal dryness | 2.2 | 2.0 |
| Respiratory, thoracic and mediastinal disorders | ||
| Cough | 6.1 | 5.0 |
| Pharyngolaryngeal pain | 3.9 | 2.5 |
| Nasal congestion | 2.2 | 2.0 |
- Paget’s disease of bone
Adverse reactions suspected (investigator assessment) to be drug related and occurring in at least 2% of the Paget’s patients receiving zoledronic acid injection (single, 5 mg, intravenous infusion) or risedronate (30 mg, oral, daily dose for 2 months) over a 6-month study period are listed by system organ class in Table 6.
Table 6: Adverse reactions suspectedª to be drug related occurring in at least 2% of Paget’s patients receiving zoledronic acid injection (single 5 mg i.v. infusion) or risedronate (oral 30 mg daily for 2 months) over a 6-month follow-up period
single 5 mg i.v. zoledronic acid injection administration | 30 mg/day x 2 months risedronate | |
| System organ class | % (N = 177) | % (N = 172) |
Metabolism and nutrition disorders Hypocalcemia | 3 | 1 |
Nervous system disorders Headache | 7 | 4 |
| Lethargy | 4 | 1 |
Gastrointestinal disorders Diarrhea | 2 | 0 |
| Nausea | 6 | 2 |
| Dyspepsia | 2 | 2 |
Infections and infestations Influenza | 3 | 0 |
Musculoskeletal, connective tissue and bone disorders Myalgia | 6 | 4 |
| Bone pain | 5 | 1 |
| Arthralgia | 4 | 2 |
General disorders and administrative site conditions Influenza-like illness | 9 | 5 |
| Pyrexia | 7 | 1 |
| Rigors | 7 | 1 |
| Fatigue | 5 | 2 |
| Pain | 3 | 2 |
| Asthenia | 2 | 1 |
Respiratory, thoracic and mediastinal disorders Dyspnea | 2 | 0 |
| a Investigator assessment |
Table 7: Most frequent adverse reactions occurring in at least 5% of Paget’s patients in any group receiving zoledronic acid injection (single 5 mg i.v. infusion) or risedronate (oral 30 mg daily for 2 months) by time of occurrence
AE occurrence ≤ 3 days after treatment initiation
AE occurrence > 3 days after treatment initiation
System organ class
Single 5 mg i.v. zoledronic acid injection administration
30 mg/day x
2 months risedronate
single 5 mg i.v. zoledronic acid injection administratio n
30 mg/day x
2 months risedronate
%
(N = 177)
%
(N = 172)
%
(N = 177)
%
(N = 172)
Nervous system disorders
Headache
7
4
4
6
Dizziness
3
1
5
3
Gastrointestinal disorders
Diarrhea
2
1
4
5
Nausea
6
2
3
5
Infections and infestations
Nasopharyngitis
1
0
5
8
Musculoskeletal, connective tissue and bone disorders
Myalgia
7
4
1
1
Bone pain
5
1
4
4
Arthralgia
5
0
5
11
Back pain
2
1
2
7
Pain in extremity
0
1
7
7
General disorders and administrative site conditions
Influenza-like illness
10
4
1
2
Pyrexia
7
1
1
1
Rigors
7
1
1
1
Fatigue
7
2
2
2
Local reactions: In the postmenopausal osteoporosis trial, local reactions at the infusion site such as itching, redness and/or pain have been reported in 0.7% of patients following the administration of zoledronic acid injection and 0.5% of patients following the administration of placebo. In the male osteoporosis trial, the event rate was 2.6% in the zoledronic acid treatment group and 1.4% in the alendronate treatment group. In the prevention of postmenopausal osteoporosis trial, the event rate was 1.1% in zoledronic acid injection treated patients compared to 2.0% in placebo treated patients.
Iritis/uveitis/episcleritis/conjunctivitis: Cases of iritis/uveitis/episcleritis/conjunctivitis have been reported in patients treated with bisphosphonates, including zoledronic acid. In the postmenopausal osteoporosis trial, 9 (0.2%) patients treated with zoledronic acid injection and 1 (< 0.1%) patient treated with placebo developed iritis/uveitis/episcleritis. Of the ocular conditions known to be related to bisphosphonate use, one case of iritis in a zoledronic acid-treated patient was reported in the HORIZON-RFT trial. In the male osteoporosis trial, two cases of conjunctivitis and one case of eye pain were reported in zoledronic acid-treated patients. In addition, one case of iritis was reported in the alendronate group. One case of conjunctivitis in a zoledronic acid- treated patient was reported in the glucocorticoid-induced osteoporosis trial. In the prevention of postmenopausal osteoporosis trial, conjunctivitis was reported in two patients (1.1%) in the zoledronic acid group. Uveitis/iritis was reported in 3 patients (1.7%) in the zoledronic acid group and in no patients (0%) in the placebo group.
Renal impairment: In the postmenopausal osteoporosis HORIZON-PFT trial, zoledronic acid has been associated with renal impairment manifested as deterioration in renal function (i.e. increased serum creatinine) and in rare cases acute renal failure (see Table 8). In the clinical trial for postmenopausal osteoporosis, patients with baseline creatinine clearance < 30 mL/min, urine dipstick ≥ 2+ protein or increase in serum creatinine of > 0.5 mg/dL (44.2 mcmol/L) during the screening visits were excluded. Overall, there was a transient increase in serum creatinine observed within 10 days of dosing in 42 (1.8%) zoledronic acid injection-treated patients versus 19 (0.8%) placebo-treated patients which resolved without specific therapy. Severe renal impairment was rarely reported, and in most of these patients recovery was not achieved by the end of the trial. Adjudicated changes in renal function and renal adverse events over the 3 year trial are described in Tables 8 and 9.
Table 8: Adverse renal events associated with change in renal function confirmed by adjudication, regardless of study drug relationship, by preferred term (safety population of the HORIZON-PFT trial)
| Preferred term | Zoledronic acid injection (N=3862) n (%) | Placebo (N=3852) n (%) |
| Total | 90 (2.33) | 74 (1.92) |
| Creatinine decreased renal clearance | 29 (0.75) | 33 (0.86) |
| Blood creatinine increased | 22 (0.57) | 6 (0.16) |
| Renal failure | 16 (0.41) | 14 (0.36) |
| Renal impairment | 11 (0.28) | 20 (0.52) |
| Proteinuria | 9 (0.23) | 6 (0.16) |
| Renal failure acute | 9 (0.23) | 2 (0.05) |
| Renal failure chronic | 1 (0.03) | 2 (0.05) |
| Azotemia | 4 (0.10) | 0 (0.00) |
Table 9: Change in renal function confirmed by adjudication, safety population of the HORIZON-PFT trial
Zoledronic acid (N=3862) | Placebo (N=3852) | |||
| n | (%) | n | (%) | |
| Overall | 178 | (4.6) | 157 | (4.1) |
| Renal adverse event | 175 | (4.5) | 154 | (4.0) |
| Increase in serum creatinine >0.5 mg/dL | 55 | (1.4) | 41 | (1.1) |
| Calculated creatinine clearance <30 mL/min | 62 | (1.6) | 57 | (1.5) |
| Baseline calculated creatinine clearance ≤60 mL/min and declined by ≥30% | 114 | (3.0) | 115 | (3.0) |
N = the number of patients in the analysis population n = the number of patients with the event (%) = n/N * 100 |
In the HORIZON-PFT trial, the change in creatinine clearance (measured annually prior to dosing), and the incidence of renal failure and impairment was comparable for both the zoledronic acid injection and placebo treatment groups over 3 years.
In the male osteoporosis trial, the incidence of confirmed renal adverse events was higher in the zoledronic acid group (4.6%) relative to the alendronate group (1.4%). There was a transient increase in serum creatinine from baseline (> 0.5 mg/dL) observed 9-11 days post-infusion in 7 (4.6%) zoledronic acid-treated patients versus 1 (0.7%) alendronate-treated patient which subsequently decreased to baseline or near baseline levels. Adjudicated changes in renal function and renal adverse events over the 2 year trial are described in tables 10 and 11.
Table 10: Change in renal function confirmed by adjudication, safety population of male osteoporosis trial
Zoledronic Acid N=153 n (%) | Alendronate N=148 n (%) | |
| Overall | 7 (4.6) | 2 (1.4) |
| Renal adverse event | 7 (4.6) | 2 (1.4) |
| Increase in serum creatinine > 0.5 mg/dL | 7 (4.6) | 1 (0.7) |
| Creatinine clearance < 30 mL/min | 2 (1.3) | 1 (0.7) |
| Baseline calculated creatinine clearance ≤60 and declined ≥ 30% | 5 (3.3) | 1 (0.7) |
| Significant proteinuria | 1 (0.7) | 0 (0.0) |
- N = the number of patients in the analysis population
- n = the number of patients with the event
(%) = n/N * 100
Table 11: Adverse renal events associated with change in renal function, regardless of study drug relationship, by preferred term (safety population of male osteoporosis trial)
| Preferred term | Zoledronic acid injection (N=153) n (%) | Alendronate (N=148) n (%) |
| Total | 7 (4.6) | 6 (4.1) |
| Blood creatinine increased | 3 (2.0) | 1 (0.7) |
| Renal impairment | 2 (1.3) | 1 (0.7) |
| Azotemia | 1 (0.7) | 0 |
| Proteinuria | 1 (0.7) | 0 |
| Renal failure | 1 (0.7) | 1 (0.7) |
| Creatinine renal clearance decreased | 0 | 2 (1.4) |
| Renal failure acute | 0 | 1 (0.7) |
In the glucocorticoid-induced osteoporosis trial, the incidence of confirmed renal adverse events was 2.2% for zoledronic acid-treated patients versus 1.4% for risedronate-treated patients. There was a greater incidence of confirmed increases in serum creatinine from baseline (> 0.5% mg/dL) observed in 9 (2.2%) zoledronic acid-treated patients compared to 3 (0.7%) risedronate- treated patients. Adjudicated laboratory changes in renal function and renal adverse events over the one year trial are described in table 12. In addition, the incidence of renal failure was 0.7% in the zoledronic acid patients and 0.0% in the risedronate patients and the incidence of acute renal failure was 0.2% in the zoledronic acid patients and 0.5% in the risedronate patients.
Table 12: Renal laboratory criteria confirmed as a significant renal adverse event by adjudication (GIO safety population)
Zoledronic Acid N = 416 n (%) | Risedronate N = 417 n (%) | |
| Overall | 9 (2.2) | 6 (1.4) |
| Renal adverse event* | 9 (2.2) | 6 (1.4) |
| Increase in serum creatinine > 0.5 mg/dL (1) | 9 (2.2) | 3 (0.7) |
| Creatinine clearance < 30 mL/min | 1 (0.2) | 0 (0.0) |
| Baseline CrCl ≤60 and declined ≥30% | 0 (0.0) | 1 (0.2) |
| Significant proteinuria | 3 (0.7) | 2 (0.5) |
- N = the number of patients in the analysis population
- n=the number of patients with the event
(%) = 100*n/N
* The adjudication committee determined that a clinically significant renal adverse event had occurred independent of an event being reported by the investigator.
In the prevention of postmenopausal osteoporosis trial, one zoledronic acid-treated patient (0.6%) reported a creatinine clearance value of <30 mL/min. One zoledronic acid-treated patient (0.6%) reported a creatinine clearance value of <30 mL/min and a ≥30% decline in CrCl during the study from a baseline value of ≤60 mL/min. One zoledronic acid-treated patient (0.6%) had renal failure confirmed by adjudication. No patients in the placebo group had renal failure, acute renal failure, or decreased CrCl.
Bronchoconstriction in ASA (acetylsalicylic acid) Sensitive Asthma Patients: While not observed in clinical trials with zoledronic acid injection there have been previous reports of bronchoconstriction in ASA-sensitive patients receiving bisphosphonates.
Osteonecrosis of the Jaw (ONJ): In the postmenopausal osteoporosis trial (HORIZON-PFT) in 7,736 patients, symptoms consistent with ONJ occurred in one patient treated with zoledronic acid injection and one patient treated with placebo. Both cases resolved after appropriate treatment. ONJ has not been observed in the HORIZON-RFT, the male osteoporosis, the glucocorticoid-induced osteoporosis, the prevention of postmenopausal osteoporosis, or the Paget’s disease trials with zoledronic acid injection.
Avascular necrosis and delayed fracture union/non-union: In the postmenopausal osteoporosis trial, 3 cases (2 zoledronic acid, 1 placebo patients) were confirmed to be cases of delayed union of fracture, one of which occurred in a patient with fracture that pre-existed at baseline. 7 cases of avascular necrosis (zoledronic acid = 4, placebo = 3) were reported (6 cases occurred in the hip region and 1 case was in the knee region). In the HORIZON-RFT trial, 3 (0.3%) patients had confirmed events of delayed union/non-union in the zoledronic acid group (2 incident hip and 1 humerus) and 3 (0.3%) patients had confirmed events in the placebo group (1 incident hip, 1 contralateral hip, and 1 shoulder). Six (0.6%) patients in the zoledronic acid group and 3 (0.3%) patients in the placebo group had confirmed events of avascular necrosis, all of which involved the hip. In the glucocorticoid-induced osteoporosis trial, 5 cases of avascular necrosis (zoledronic acid = 2 and risedronate = 3) were reported.
Abnormal Hematologic and Clinical Chemistry Findings
Serum creatinine and creatinine clearance
- Postmenopausal osteoporosis
A transient increase in serum creatinine (> 0.5 mg/dL (44.2 mcmol/L)) was observed within 10 days following administration in 42 (1.8%) zoledronic acid injection-treated patients versus 19 (0.8%) placebo-treated patients (see ADVERSE REACTIONS, Renal impairment).
Severe renal dysfunction was rarely reported, and in most of these patients recovery was not achieved by the end of the trial. Adjudicated changes in renal function and renal adverse events over the 3 year trial are described in Tables 8 and 9 (see ADVERSE REACTIONS).
- Osteoporosis in men
There was a transient increase in serum creatinine from baseline (> 0.5 mg/dL) observed 9-11 days post-infusion in 7 (4.6%) zoledronic acid-treated patients versus 1 (0.7%) alendronate- treated patient which subsequently decreased to baseline or near baseline levels. Adjudicated changes in renal function and renal adverse events over the two year trial are described in Tables 10 and 11 (see ADVERSE REACTIONS).
- Glucocorticoid-induced osteoporosis
Confirmed increases in serum creatinine from baseline (> 0.5% mg/dL) were observed in 9 (2.2%) zoledronic acid-treated patients compared to 3 (0.7%) risedronate-treated patients. Adjudicated laboratory changes in renal function and renal adverse events over the one year trial are described in Table 12.
- Paget’s disease of bone
No clinically significant changes in serum creatinine have occurred in the Paget’s disease trials.
Hypocalcemia
- Postmenopausal osteoporosis
In the postmenopausal osteoporosis trial (HORIZON-PFT), mild, transient, asymptomatic decrease in calcium levels, have been observed with zoledronic acid injection primarily after the first dose. Approximately 0.2% of patients had notable declines of serum calcium levels (less than 1.87 mmol/L) following zoledronic acid injection administration. No symptomatic cases of hypocalcaemia were observed. In this trial, patients received supplemental daily doses of elemental calcium (1000 to 1500 mg) and vitamin D (400 to 1200 IU).
In the prevention of postmenopausal osteoporosis trial, one patient (0.5%) treated with zoledronic acid injection (administered at randomization and at Month 12, see CLINICAL TRIALS) had a confirmed event of hypocalcemia with a notable decline of calcium level of 1.70 mmol/L from a screening value of 2.17 mmol/L one month following the first infusion of zoledronic acid injection.
- Paget’s disease of bone
In the Paget’s disease trials, early, transient decreases in serum calcium and phosphate levels, that were usually asymptomatic, have been observed. Approximately 21% of subjects had serum calcium levels <2.1 mmol/L (<8.4 mg/dL) 9-11 days following zoledronic acid injection infusion. In the Paget’s disease trials, symptomatic hypocalcemia was observed in approximately 1% of patients, all of which resolved.
In the HORIZON-RFT, the male osteoporosis, or the glucocorticoid induced-osteoporosis trials, there were no patients who had treatment emergent serum calcium levels below 1.87 mmol/L.
Post-Market Adverse Drug Reactions
Because these events are reported voluntarily from a population of uncertain size, it is not always possible to reliably estimate their frequency or clearly establish a causal relationship to zoledronic acid injection exposure.
Cardiovascular: Atrial fibrillation, cerebrovascular accident, some with a fatal outcome (see WARNINGS AND PRECAUTIONS).
Eye disorders: Orbital inflammation, scleritis, uveitis, conjunctivitis, iritis, episcleritis (see WARNINGS AND PRECAUTIONS).
General disorders and administration site conditions: Fever, flu-like symptoms (pyrexia, asthenia, fatigue, or malaise) persisting for greater than 30 days.
Immune system disorders: Hypersensitivity, bronchoconstriction, urticaria, angioedema, and anaphylactic reactions/shock (rarely)
Metabolism and nutrition disorders: Hypocalcaemia, dehydration, hypophosphatemia
Musculoskeletal and connective tissue disorders: Arthralgia, myalgia, low-energy femoral shaft fractures, osteonecrosis of the jaw, osteonecrosis of other bones (femur, hip, knee, humerus and external auditory canal) (see WARNINGS AND PRECAUTIONS).
Nervous system disorders: Headache
Renal and urinary disorders: Renal failure requiring dialysis or with fatal outcome. Increased serum creatinine was reported in patients with 1) underlying renal disease, 2) dehydration secondary to fever, sepsis, gastrointestinal losses, or diuretic therapy, or 3) other risk factors such as advanced age, or concomitant nephrotoxic drugs in the post-infusion period (see WARNINGS AND PRECAUTIONS).
Vascular disorders: Hypotension
DRUG INTERACTIONS
Overview
Zoledronic acid is not metabolized in humans. Zoledronic acid is eliminated by renal excretion (see PART II, ACTION AND CLINICAL PHARMACOLOGY, Pharmacokinetics).
Drug-Drug Interactions
No in vivo drug interaction studies have been performed for zoledronic acid injection. In vitro and ex vivo studies showed low affinity of zoledronic acid for the cellular components of human blood. In vitro mean zoledronic acid protein binding in human plasma ranged from 28% at 200 ng/mL to 53% at 50 ng/mL. In vivo studies showed that zoledronic acid is not metabolized, and is excreted into the urine as the intact drug.
Table 13: Established or Potential Drug-Drug Interactions
| Zoledronic acid | Ref | Effect | Clinical comment |
| Aminoglycosides | T | ↓ serum calcium level | Caution is advised when bisphosphonates, including zoledronic acid, are administered with aminoglycosides, since these agents may have an additive effect to lower serum calcium level for prolonged periods. This effect has not been reported in zoledronic acid clinical trials. |
| Loop Diuretics | T | ↑ risk of hypocalcemia | Caution should also be exercised when Zoledronic Acid Injection is used in combination with loop diuretics due to an increased risk of hypocalcemia. |
| Nephrotoxic Drugs | T | Caution is indicated when Zoledronic Acid Injection is used with other potentially nephrotoxic drugs such as nonsteroidal anti-inflammatory drugs. | |
| Drugs primarily excreted by the kidney | T | ↑ systemic exposure | In patients with renal impairment, the systemic exposure to concomitant medicinal products that are primarily excreted via the kidneys may increase |
| Calcitonin | T | ↓ serum calcium level/Hypocalcemia | Concomitant administration of Zoledronic Acid Injection and calcitonin may increase the risk of hypocalcemia. Use with caution. |
| Angiogenesis inhibitor | T | Osteonecrosis of jaw | Concomitant administration of Zoledronic Acid injection and angiogenesis inhibitors may increase the risk of developing ONJ. Caution should be exercised. Patients taking angiogenesis inhibitors should have a dental exam prior to treatment with Zoledronic Acid Injection (see WARNINGS AND PRECAUTIONS, Musculoskeletal). |
(Legend: CT = Clinical Trial; T = Theoretical)
Drug-Food Interactions
The interaction of zoledronic acid has not been studied with regards to food.
Drug-Herb Interactions
The interaction of zoledronic acid with herbal medications or supplements has not been studied.
Drug-Laboratory Interactions
No data suggest that zoledronic acid interferes with laboratory tests.
Drug-Lifestyle Interactions
Specific drug-lifestyle interaction studies have not been conducted with zoledronic acid.
DOSAGE AND ADMINISTRATION
Recommended Dose and Dosage Adjustment
Treatment of postmenopausal osteoporosis
The recommended dose is a once yearly single intravenous infusion of Zoledronic Acid Injection.
Treatment to increase bone mineral density in men with osteoporosis
The recommended dose is a once yearly single intravenous infusion of Zoledronic Acid Injection.
Treatment and prevention of glucocorticoid-induced osteoporosis, to increase bone mineral density
The recommended dose is a once yearly single intravenous infusion of Zoledronic Acid Injection.
Prevention of postmenopausal osteoporosis
The recommended dose is a single intravenous infusion of Zoledronic Acid Injection.
Re-treatment for prevention of postmenopausal osteoporosis
Specific re-treatment data after 24 months are not available. After one treatment with zoledronic acid injection 5 mg intravenous infusion in the prevention of postmenopausal osteoporosis trial, the effect on lumbar spine BMD was observed for up to 24 months (see CLINICAL TRIALS, Table 25). There are no clinical efficacy data available beyond the 24 months’ duration of the trial.
Treatment of Paget's disease of bone
The recommended dose is a single intravenous infusion of Zoledronic Acid Injection.
Re-treatment of Paget’s disease
After the initial treatment with zoledronic acid injection in Paget’s disease, an extended remission period is observed in responding patients. Re-treatment consists of one additional intravenous infusion of 5 mg Zoledronic Acid Injection after an interval of one year or longer from initial treatment in patients who have relapsed. Limited data on re-treatment of Paget’s disease are available (see CLINICAL TRIALS).
Zoledronic Acid Injection (5 mg / 100 mL ready to infuse solution) is administered via a separate infusion line.
Patients should be advised to be appropriately hydrated before the administration of Zoledronic Acid Injection.
The infusion time must not be less than 15 minutes (see WARNINGS AND PRECAUTIONS) and the infusion rate should be constant. Zoledronic Acid Injection should only be given by intravenous infusion. The total volume of Zoledronic Acid Injection solution should be infused. Zoledronic Acid Injection must never be given as a bolus injection.
Renal
The use of Zoledronic Acid Injection in patients with severe renal impairment (creatinine clearance < 35mL/min) is contraindicated. Zoledronic Acid Injection should be used with caution in patients with mild to moderate renal impairment. There are no safety and efficacy data to support the adjustment of the zoledronic acid injection dose based on baseline renal function. Therefore, no dosage adjustment is required in patients with a creatinine clearance of ≥ 35 mL/min (see WARNINGS AND PRECAUTIONS). Patients must be appropriately hydrated prior to administration of Zoledronic Acid Injection, and this is especially important for patients receiving diuretic therapy (see CONTRAINDICATIONS and WARNINGS AND PRECAUTIONS).
Calcium and vitamin D intake
It is strongly advised that patients receive adequate calcium and vitamin D supplementation especially in the days before and following Zoledronic Acid Injection administration (see WARNINGS AND PRECAUTIONS). All patients should be counseled regarding the importance of calcium and vitamin D supplementation in maintaining serum calcium levels, and on the symptoms of hypocalcemia. The recommended daily vitamin D supplement should be determined by the treating physician based on the patient's individual needs. In the postmenopausal osteoporosis trial (HORIZON-PFT), patients received 1000 to 1500 mg of elemental calcium plus 400 to 1200 IU of vitamin D supplements per day.
Post-Infusion Management
About 25% of patients experienced transient post-dose symptoms within the first 3 days of their zoledronic acid injection infusion (see ADVERSE REACTIONS). Symptomatic management can be considered on an individual basis. No anaphylactic reactions have been observed in the clinical trials but good medical practice dictates caution (see CONTRAINDICATIONS).
Dosing Considerations
The optimal duration of bisphosphonate treatment for osteoporosis has not been established. The need for continued treatment should be re-evaluated periodically based on the benefits and potential risks of Zoledronic Acid Injection on an individual patient basis.
Administration
Zoledronic Acid Injection premix in single-use flexible containers does not require further dilution.
Tear the outer wrap at the notch and remove the solution container. The container is a dual port bag. The administration port at the bottom is closed with a grey rubber stopper.
Use sterile equipment.
The flexible container is for single use only. Any unused solution should be discarded.
Check the container for minute leaks by squeezing the inner bag firmly. If leaks are found, or if the seal is not intact, discard the solution, as the sterility may be compromised. Do not use if the solution is cloudy or a precipitate is present.
OVERDOSAGE
For the most recent information in the management of a suspected drug overdose, contact your regional poison control center or Health Canada’s toll-free number, 1-844 POISON-X (1-844-764-7669).
Clinical experience with acute overdose with zoledronic acid injection is limited. Patients who have received doses higher than those recommended should be carefully monitored. In the event of clinically significant hypocalcemia, reversal may be achieved with supplemental oral calcium and vitamin D and/or an infusion of calcium gluconate.
ACTION AND CLINICAL PHARMACOLOGY
Mechanism of Action
Zoledronic acid belongs to the class of nitrogen containing bisphosphonates and acts primarily on bone in order to protect the bone against excessive and abnormal osteoclastic and osteoblastic activity. It is an inhibitor of osteoclast-mediated bone resorption.
The selective action of bisphosphonates on bone is based on their high affinity for mineralized bone. Intravenously administered zoledronic acid rapidly partitions to bone and, as with other bisphosphonates, localizes preferentially at sites of high bone turnover. The main molecular target of zoledronic acid in the osteoclast is the enzyme farnesyl pyrophosphate synthase (FPP) which is critical for the regulation of a variety of cell processes important for osteoclast function, but this does not exclude other inhibitory mechanisms. In vitro assays have demonstrated that zoledronic acid has the highest potency to inhibit FPP synthase amongst available nitrogen containing bisphosphonates. This higher inhibition of FPP synthase correlated with a greater anti-resorptive potency as observed in vivo in rats. The relatively long duration of action of zoledronic acid is attributable to its high binding affinity for the active site of farnesyl pyrophosphate (FPP) synthase and its strong binding affinity to bone mineral.
Pharmacodynamic effects
In long-term animal studies, zoledronic acid inhibits bone resorption without adversely affecting bone formation, mineralization or mechanical properties of bone. Histomorphometric data from long-term rat and monkey studies showed the typical response of bone to an anti-resorptive agent with a dose-dependent reduction in osteoclastic activity and in activation frequency of new remodeling sites in both trabecular and haversian bone. Continuing bone remodeling was observed in bone samples from all animals treated with clinically relevant doses of zoledronic acid. There was no evidence of a mineralizing defect, no aberrant accumulation of osteoid, and no woven bone in treated animals.
Bone histology and bone markers
- Postmenopausal osteoporosis
Dynamic bone histomorphometry was evaluated in 93 postmenopausal patients with osteoporosis after being treated with 3 annual doses of zoledronic acid injection. These results showed bone of normal quality with no evidence of impaired bone remodeling and no evidence of mineralization defects.
Microcomputed tomography analysis demonstrated preservation of trabecular bone architecture in patients treated with zoledronic acid injection compared to placebo. In summary, the bone biopsies and biomarkers indicate ongoing bone remodeling with qualitatively normal bone.
In the osteoporosis treatment trial, the effect of zoledronic acid injection treatment on markers of bone resorption (serum beta-C-telopeptides (b-CTx)) and bone formation (bone specific alkaline phosphatase (BSAP), serum N-terminal propeptide of type I collagen (P1NP)) was evaluated in patients (subsets ranging from 517 to 1,246 patients) at periodic intervals. Treatment with a 5 mg annual dose of zoledronic acid injection reduces bone turnover markers to the pre-menopausal range with an approximate 55% reduction in b-CTx, a 29% reduction in BSAP and a 52% reduction in P1NP over 36 months. There was no progressive reduction of bone turnover markers with repeated annual dosing.
Zoledronic acid injection treatment rapidly reduced the rate of bone turnover from elevated postmenopausal levels with the nadir for resorption markers observed at 7 days, and for formation markers at 12 months. Thereafter bone markers stabilized within the pre-menopausal range. There was no progressive reduction of bone turnover markers with repeated annual dosing.
- Glucocorticoid-induced osteoporosis
Bone biopsy specimens were obtained at month 12 from 23 patients treated with either an annual dose of zoledronic acid injection or daily oral risedronate (12 in the zoledronic acid injection treatment group and 11 in the risedronate treatment group). All biopsies were adequate for qualitative histomorphometry assessment. Qualitative and quantitative assessments showed bone of normal architecture and quality without mineralization defects.
- Paget’s disease
Bone histology was evaluated in 7 patients with Paget’s disease 6 months after being treated with zoledronic acid injection. Bone biopsy results showed bone of normal quality with no evidence of impaired bone remodeling and no evidence of mineralization defect. These results were consistent with biochemical marker evidence of normalization of bone turnover.
Pharmacokinetics
Pharmacokinetic data in patients with postmenopausal osteoporosis, osteoporosis and Paget's disease of bone are not available.
Distribution: Single or multiple (q 28 days) 5-minute or 15-minute infusions of 2, 4, 8 or 16 mg zoledronic acid were given to 64 cancer patients with bone metastases. The post-infusion decline of zoledronic acid concentrations in plasma was consistent with a triphasic process showing a rapid decrease from peak concentrations at end-of-infusion to <1% of Cmax 24 hours post infusion with population half-lives of t1/2α 0.24 hours and t1/2β 1.87 hours for the early disposition phases of the drug. The terminal elimination phase of zoledronic acid was prolonged, with very low concentrations in plasma between days 2 and 28 post infusion, and an estimated terminal elimination half-life t1/2γ of 146 hours. The area under the plasma concentration versus time curve (AUC0-24h) of zoledronic acid was dose proportional from 2 to 16 mg. The accumulation of zoledronic acid measured over three cycles was low, with mean AUC0-24h ratios for cycles 2 and 3 versus 1 of 1.13 ± 0.30 and 1.16 ± 0.36, respectively.
In vitro and ex vivo studies showed low affinity of zoledronic acid for the cellular components of human blood. Binding to human plasma proteins was approximately 43-55% at 50 ng/mL, a concentration of zoledronic acid within the range observed after 15 minute infusion of the 5 mg dose. It was only slightly less (about 43%) at 500 ng/mL a concentration of zoledronic acid greater than the expected Cmax. Therefore, interactions resulting from displacement of highly protein-bound drugs are unlikely.
Metabolism: Zoledronic acid is not metabolized in humans. It was found to have little or no capacity as a direct acting and/or irreversible metabolism-dependent inhibitor of P450 enzymes.
Therefore, zoledronic acid is unlikely to reduce the metabolic clearance of substances which are metabolized via the cytochrome P450 enzyme systems. In animal studies, <3% of the administered intravenous dose was found in the feces, with the balance either recovered in the urine or taken up by bone, indicating that the drug is eliminated intact via the kidney.
Excretion: In 64 patients, on average 39 ± 16% (± SD) of the administered zoledronic acid dose was recovered in the urine within 24 hours with only trace amounts of drug found in urine after 48 hours. The cumulative percentage of drug excreted in the urine over 0-24 hours was independent of dose. The balance of drug not recovered in urine over 0-24 hours, representing drug presumably bound to bone, is slowly released back into the systemic circulation, giving rise to the observed prolonged low plasma concentrations. The 0-24 hour renal clearance of zoledronic acid was 3.7 ± 2.0 L/h (± SD).
Zoledronic acid clearance was independent of dose but dependent upon the patient’s creatinine clearance. In a study with patients, increasing the infusion time of a 4 mg dose of zoledronic acid from 5 minutes (n=5) to 15 minutes (n=7) resulted in a 34% decrease in the zoledronic acid plasma concentration at the end of the infusion ([mean ± SD] 403 ± 118 ng/mL vs. 264 ± 86 ng/mL) and a 10% increase in the total AUC (378 ± 116 ng x h/mL vs. 420 ± 218 ng x h/mL). The difference between the AUC means was not statistically significant.
Special Populations and Conditions
Pediatrics: Pharmacokinetic data of zoledronic acid in pediatric patients are not available.
Geriatrics: The pharmacokinetics of zoledronic acid were not affected by age in patients who ranged in age from 38 years to 84 years.
Gender: The pharmacokinetics of zoledronic acid were not affected by gender.
Race: The pharmacokinetics of zoledronic acid were not affected by race.
Hepatic Insufficiency: No clinical studies were conducted to evaluate the effect of hepatic impairment on the pharmacokinetics of zoledronic acid. Zoledronic acid does not inhibit human P450 enzymes in vitro, shows no biotransformation, suggesting no relevant role of liver function in the pharmacokinetics of zoledronic acid and no required dosage adjustment. Following an intravenous dose of 20 nCi 14C-zoledronic acid in a patient with cancer and bone metastases, only a single radioactive species with chromatographic properties identical to those of parent drug was recovered in urine, which suggests that zoledronic acid is not metabolized.
Renal Insufficiency: The pharmacokinetic studies conducted in 64 patients represented typical clinical populations with normal to moderately impaired renal function. Compared to patients with normal renal function (creatinine clearance > 80 mL/min, N=37), patients with mild renal impairment (creatinine clearance =50 to 80 mL/min, N=15) showed an average increase in plasma AUC of 15%, whereas patients with moderate renal impairment (creatinine clearance =30 to 50 mL/min, N=11) showed an average increase in plasma AUC of 43%. No dosage adjustment is required in patients with a creatinine clearance of ≥ 30 mL/min. Based on population PK/PD modeling, the risk of renal deterioration appears to increase with AUC, the risk is doubled at a creatinine clearance of 10 mL/min. Zoledronic Acid Injection is contraindicated in patients with severe renal impairment (creatinine clearance < 35 mL/min) due to an increased risk of renal failure in this population (see CONTRAINDICATIONS and WARNINGS AND PRECAUTIONS). Zoledronic Acid Injection should be used with caution in patients with mild to moderate renal impairment.
STORAGE AND STABILITY
Store Zoledronic Acid Injection at room temperature between 15°C-30°C.
Store with protective overwrap and use immediately after opening (puncturing the rubber stopper).
SPECIAL HANDLING INSTRUCTIONS
Note: Parenteral drug products should be inspected visually for particulate matter and discoloration prior to administration, whenever solution and container permit.
- Solution does not need to be diluted before administration.
- Strict adherence to the intravenous route is recommended for the parenteral administration of Zoledronic Acid Injection.
- The entire volume in the bag should be administered.
Compatibility
- Zoledronic Acid Injection must not be allowed to come in contact with any calcium- or other divalent cations-containing solutions, and it should be administered as a single dose through a separate infusion line.
- Zoledronic Acid Injection is considered to be compatible with the typical infusion line materials polyvinylchloride (PVC), polyurethane (PUR) and polyethylene (PE).
DOSAGE FORMS, COMPOSITION AND PACKAGING
Zoledronic Acid Injection, 5 mg / 100 mL is available as a ready-to-use solution for intravenous infusion in a colorless plastic bag with an aluminum overwrap. The sterile solution has a pH between 6.0 to 7.0. Each 100 mL bag contains 5.330 mg zoledronic acid monohydrate (equivalent to 5 mg zoledronic acid on an anhydrous basis), 4950 mg of mannitol, 30 mg of sodium citrate, and 100 mL water for injection.
The administration port of the plastic bag is sealed with a grey rubber stopper which is held in place with an aluminum cap. The stopper is made of chlorobutyl rubber. The stopper is not made with natural rubber latex.
PART II: SCIENTIFIC INFORMATION
PHARMACEUTICAL INFORMATION
Drug Substance
Common name: Zoledronic acid monohydrate
Chemical name: (1-Hydroxy-2-imidazol-1-ylethylidene) disphosphonic acid monohydrate
Molecular formula: C5H10N2O7P2 • H2O
Molecular mass: 290.1 g/mol
Structural formula:
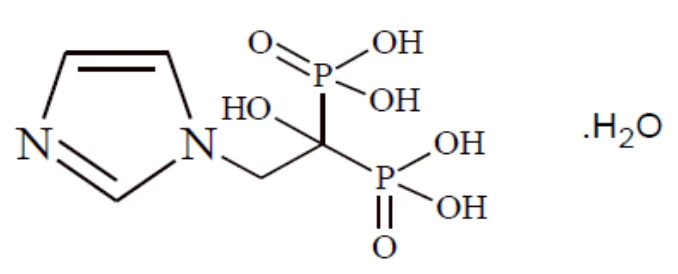
Physicochemical properties: Zoledronic acid monohydrate is a white crystalline powder.
Zoledronic acid monohydrate is slightly soluble in water, and practically insoluble in anhydrous ethanol and in heptane. The pH of a 0.3% solution of zoledronic acid in water is approximately 2.0.
CLINICAL TRIALS
Postmenopausal osteoporosis
Study demographics and trial design
The efficacy and safety of zoledronic acid injection were demonstrated in a Pivotal Fracture Trial (PFT) for the treatment of osteoporosis in postmenopausal women (HORIZON-PFT: Health Outcomes & Reduced Incidence with Zoledronic Acid Once Yearly – Pivotal Fracture Trial), a randomized, double-blind, placebo-controlled, multinational study of 7,736 women aged 65-89 years. Entry criteria were either: a femoral neck Bone Mineral Density (BMD) T- score less than or equal to - 1.5 and at least two mild or one moderate existing vertebral fracture(s); or a femoral neck BMD T-score less than or equal to -2.5 with or without evidence of an existing vertebral fracture(s).
Zoledronic acid injection was administered once a year for three consecutive years, as a single 5 mg dose in 100 mL solution infused over at least 15 minutes.
The two primary efficacy variables were the incidence of morphometric vertebral fractures at 3 years, and the incidence of hip fractures over a median duration of 3 years. Participants were placed into 1 of 2 treatment strata (Stratum I and Stratum II). 7,736 women were evaluated for the incidence of hip and all clinical fractures. All clinical fractures were verified based on the radiographic and/or clinical evidence. Of these, 5,661 women were evaluated annually for incidence of vertebral fractures. In Stratum I, women who were evaluated for the incidence of vertebral fractures did not receive concomitant osteoporosis therapy, which was allowed for women contributing to the hip and all clinical fracture evaluations in Stratum II. Concomitant osteoporosis therapy included: calcitonin, raloxifene, tamoxifen, hormone replacement therapy, tibolone (not approved in Canada); but excluded other bisphosphonates. All women received 1000 to 1500 mg of elemental calcium plus 400 to 1200 IU of vitamin D supplements per day.
Non-vertebral fractures represent fractures at sites other than the vertebral spine. Clinical fractures represent fractures that are clinically apparent and usually present with pain. These include both clinical vertebral and clinical non-vertebral fractures such as at the hip and wrist. All clinical fractures were verified based on the radiographic and/or clinical evidence. All efficacy assessments of non-vertebral fractures and clinical fractures are based on both Stratum I and Stratum II. Although morphometric vertebral fracture endpoints are based on Stratum I alone, clinical vertebral fracture because it is a clinical fracture endpoint, is assessed across both Stratum I and Stratum II.
Table 14: Summary of patient demographics for clinical trial in postmenopausal osteoporosis
| Study # | Trial design | Dosage, route of administration and duration | Study subjects (N= population treated) | Mean age (Range) | Gender Male/Female (N= randomized patients) | ||
| Zoledronic acid injection | Placebo | Zoledronic acid injection | Placebo | ||||
2301 HORIZON- PFT | Multicenter, randomized, double-blind, placebo- controlled efficacy and safety trial | Three doses of 5 mg zoledronic acid injection / 100 mL over 15 min (or placebo infusion) per 12 months Duration: 36 months | N = 3862 | N = 3852 | 73.1 (64-89) | 73.0 (64-89) | 7736 (0% male/ 100% female) |
Study results
Effect on Vertebral Fracture in the HORIZON-PFT study
Zoledronic acid injection significantly reduces the relative risk of new vertebral fractures by 70% (absolute reduction in fracture incidence 7.6% over 3 years), over three years, as compared to placebo, and this reduction was demonstrated as early as the one year timepoint (see Table 15).
Table 15: Summary of vertebral fracture efficacy at 12 months, 24 months, and 36 months (Stratum I)
| Endpoints | N | Patients with new vertebral fractures | Absolute reduction in fracture incidence % | Relative risk reduction in fracture incidence % | P-value | |||||||||
| Zoledronic acid injection | Placebo | Zoledronic acid injection n (%) | Placebo n (%) | |||||||||||
| (95% CI) | (95% CI) | |||||||||||||
| At least one new vertebral fracture (over 12 months) | 2822 | 2853 | 42 (1.5) | 106 (3.7) | 2.2 (1.4 - 3.1) | 60 (43 - 72) | < 0.0001 | |||||||
| At least one new vertebral fracture (over 24 months) | 2822 | 2853 | 63 (2.2) | 220 (7.7) | 5.5 (4.4 - 6.6) | 71 (62 - 78) | < 0.0001 | |||||||
| At least one new vertebral fracture (over 36 months) | 2822 | 2853 | 92 (3.3) | 310 (10.9) | 7.6 (6.3 - 9.0) | 70 (62 - 76) | < 0.0001 | |||||||
Zoledronic acid injection significantly decreased the relative risk of new vertebral fractures at 12 months (relative risk reduction 60%) (absolute risk reduction 2.2%), at 24 months (relative risk reduction 71%) (absolute risk reduction 5.5%), and at 36 months (relative risk reduction 70%) (absolute risk reduction 7.6%) (all p < 0.0001).
Zoledronic acid injection significantly decreased the relative risk of one or more new/worsening vertebral fractures at 1 year as compared to placebo (relative risk reduction 58%) (absolute reduction in fracture incidence 2.3%), 2 years (68%) (absolute reduction in fracture incidence 5.7%) and 3 years (68%) (absolute reduction in fracture incidence 7.9%) (all p<0.0001). Zoledronic acid injection significantly decreased the relative risk at 1 year as compared to placebo, of at least one new moderate or severe vertebral fracture at 1 year (60%; absolute reduction in fracture incidence 1.9%), 2 years (71%; absolute reduction in fracture incidence 4.6%) and 3 years (70%; absolute reduction in fracture incidence 6.6%) (all p<0.0001). Zoledronic acid injection significantly decreased the relative risk of at least 2 new vertebral fractures over 3 years as compared to placebo (89%; absolute reduction in fracture incidence 2.1%) (p<0.0001).
These reductions in vertebral fractures over three years were consistent and significantly greater than placebo regardless of age, geographical region, race, baseline body mass index, number of baseline vertebral fractures, femoral neck BMD T-score or prior bisphosphonate use. Specifically for patients aged 75 years and older, zoledronic acid injection patients had a 60% relative risk reduction in the risk of vertebral fractures (absolute reduction in fracture incidence 7.2%) compared to placebo patients (p<0.0001).
Effect on Hip fracture over 3 years in the HORIZON-PFT study
Zoledronic acid injection significantly reduced the risk of new hip fractures by 41% (RR 0.60) at 3 years compared to placebo (p= 0.0024). The hip fracture event rate was 1.45% for zoledronic acid injection-treated patients compared to 2.50% for placebo-treated patients. Zoledronic acid injection demonstrated a 1.1% absolute reduction and 41% reduction in the risk of hip fractures over a median duration of follow-up of 3 years. The incidence of first hip fracture over time is displayed in Table 16.
Table 16: Between-treatment comparison of the incidence of the first hip fracture over time (Stratum I and II)
| Treatment N | N | n (%)1 | Hazard ratio (95% CI)2 | P-value3 |
| Zoledronic acid injection | 3875 3875 | 52 (1.44) | 0.59 (0.42 -0.83) | 0.0024 |
| Placebo 3861 | 3861 | 88 (2.49) |
1 n is the number of patients with hip fracture over time, and % is Kaplan-Meier estimate of event rate at Month 36.
2 The hazard ratio of zoledronic acid injection versus placebo and the 95% confidence interval (CI) are based on a stratified Cox proportional hazards regression model with treatment as a factor and stratified by stratum. A hazard ratio < 1 implies that patients treated with zoledronic acid injection have a lower risk of experiencing a hip fracture than patients treated with placebo.
3 The p-value is calculated from a stratified log-rank test analyzed by study population stratum.
The time to first hip fracture is shown in Figure 1.
Figure 1: Cumulative risk reduction of hip fracture over 3 years (Strata I + II)
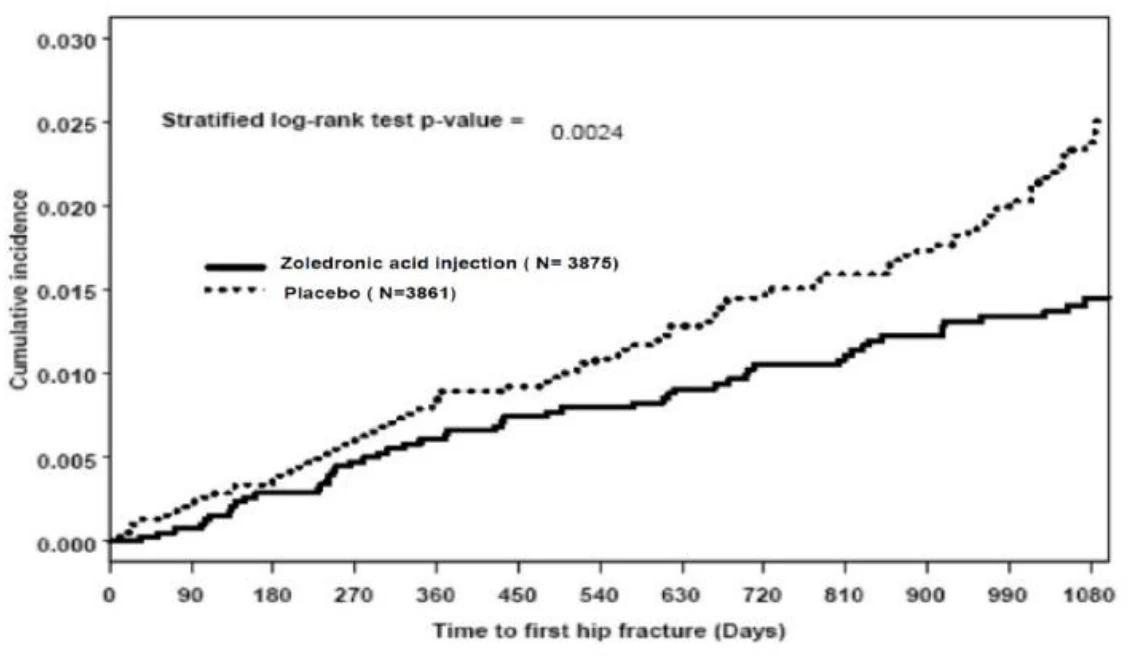
The reductions in hip fractures over three years were greater for zoledronic acid injection than placebo regardless of femoral neck BMD T-score.
Effect observed in the Stratum in the HORIZON-PFT study
Participants of the osteoporosis study were placed into one of the 2 treatment strata (Stratum I: patients not taking concomitant osteoporosis therapy and Stratum II: patients who were allowed taking concomitant osteoporosis therapy). The study was not powered a priori to evaluate differences across subgroups. However, despite this, zoledronic acid demonstrated a 51% reduction in the risk of hip fractures in patients who were bisphosphonate-naïve, this corresponds to an absolute risk reduction of 1.4% (HR=0.49, 95% CI: 0.33 to 0.72; p< 0.001). In contrast, a relatively small number of patients who were previously treated with bisphosphonates had numerically more hip fractures in the zoledronic acid treatment group (12/565 patients) compared to the placebo group (8/557 patients), this corresponds to an absolute risk increase of 0.8%. (HR=1.49, 95% CI: 0.61 to 3.64; p =0.3817).
The reductions in hip fractures over three years were greater than placebo regardless of age, geographical region, race, baseline body mass index, number of baseline vertebral fractures, or femoral neck BMD T-score.
Effect on All Clinical Fractures in the HORIZON-PFT study
Zoledronic acid injection demonstrated superiority to placebo in reducing the incidence of all clinical fractures, clinical (symptomatic) vertebral and non-vertebral fractures (excluding finger, toe, facial, and clinical thoracic and lumbar vertebral fractures). All clinical fractures were verified based on the radiographic and/or clinical evidence. A summary of results is presented in Table 17.
Table 17: Between –Treatment Comparisons of the Incidence of Clinical Fracture Variables Over 3 Years
Outcome
Zoledronic acid injection (N=3875)
Event rate n (%)
Placebo (N=3861)
Event rate n (%)
Absolute reduction in fracture incidence (%)
(95% CI)
Relative risk reduction in fracture incidence (%)
(95% CI)
Any clinical fracture (1)
308 (8.4)
456 (12.8)
4.4 (3.0, 5.8)
33 (23, 42)
p-value <0.001
Clinical vertebral
fracture (2)
19 (0.5)
84 (2.6)
2.1 (1.5, 2.7)
77 (63, 86)
p-value <0.001
Non-vertebral
fracture (3)
292 (8.0)
388 (10.7)
2.7 (1.4, 4.0)
25 (13, 36)
p-value <0.0001
- (1) Excluding finger, toe, and facial fractures
- (2) Includes clinical thoracic and clinical lumbar vertebral fractures
- (3) Excluding finger, toe, facial, and clinical thoracic and lumbar vertebral fractures
Effect on Bone Mineral Density (BMD) in the HORIZON-PFT study
Zoledronic acid injection significantly increased BMD at the lumbar spine, hip, and distal radius relative to treatment with placebo at all timepoints (6, 12, 24, and 36 months) (p< 0.0001 for all). Treatment with zoledronic acid injection resulted in an 6.7% increase in BMD at the lumbar spine, 6.0 % at the total hip, and 5.1% at the femoral neck, and 3.2% at the distal radius over 3 years as compared to placebo (p< 0.0001 for all).
Change in Patients Height in the HORIZON-PFT study
Standing height was measured annually using a stadiometer at baseline and months 12, 24 and 36. The zoledronic acid injection-treated patients had significantly less reduction in height at 3 years compared to placebo (4.2 mm vs. 6.7 mm, respectively (p< 0.0001)).
The efficacy and safety of zoledronic acid injection in the prevention of clinical fractures in osteoporotic patients who suffered a recent low-trauma hip fracture were evaluated in the prevention of clinical fractures after hip fracture trial HORIZON-RFT. This was a randomized, double-blind, placebo-controlled, multinational fracture endpoint-driven study of 2,127 men (23.88%) and women (76.12%) aged 50-95 years (mean age of 74.5) and 91% of the patients were Caucasian.
The incidence of clinical fractures, including vertebral, non-vertebral, and hip fractures, was evaluated in patients with a recent (within 90 days) low-trauma hip fracture who were followed for an average of 2 years on study drug. The following concomitant osteoporosis therapies were allowed: calcitonin, raloxifene, tamoxifen, hormone replacement therapy, tibolone, dehydroepiandrosterone (DHEA(s)), ipriflavone, and testosterone, as hormone replacement in the case of hypogonadal men; but excluded other bisphosphonates and parathyroid hormone.
Zoledronic acid injection was administered once a year as a single 5 mg dose in 100 mL solution, infused over at least 15 minutes, until at least 211 patients had confirmed clinical fractures in the study population. All participants received 1000 to 1500 mg of elemental calcium plus 800 to 1200 IU of vitamin D supplementation per day. The primary efficacy variable was the incidence of clinical fractures over the duration of the study.
Table 18: Summary of patient demographics in the HORIZON-RFT study
| Study # | Trial design | Dosage, route of administration and duration | Study subjects | Mean age (Range) | Gender Male/Female (N= randomized patients) | ||
| Zoledronic acid injection | Placebo | Zoledro nic acid injection | Placebo | ||||
2310 HORIZON- RFT | Multi- national, randomized, double- blind, placebo- controlled efficacy and safety trial | Single dose of 5 mg zoledronic acid injection / 100 mL over 15 min (or placebo infusion) per 12 months Duration: Event-driven | N = 1065 | N = 1062 | 74.4 (65-84) | 74.6 (65-849) | 2127 (23.88% male / 76.12% female) |
Effect on All Clinical Fractures in the HORIZON-RFT study
Treatment with zoledronic acid injection significantly reduced the incidence of any clinical fracture by 35%. There was also a 46% reduction in the risk of a clinical vertebral fracture; a 27% reduction in the risk for non-vertebral fractures with zoledronic acid injection. There was a non-significant 30% risk reduction for a subsequent hip fracture for the zoledronic acid injection group compared to placebo. There was a non- significant reduction in the incidence of clinical fractures in men compared to placebo, although the study was not powered to determine significance in this subgroup; the incidence of clinical fracture was 7.5% in men treated with zoledronic acid injection versus 8.7% for placebo.
Table 19 Between treatment comparisons of the incidence of key clinical fracture variables
| Outcome | Zoledronic acid injection (N=1064) event rate (%) | Placebo (N=1063) event rate (%) | Absolute reduction in fracture event rate (%) (95% CI) | Relative risk reduction in fracture incidence (%) (95% CI) | P-value |
| Any clinical fracture (1) | 8.6 | 13.9 | 5.3 (2.3, 8.3) | 35 (16, 50) | 0.001 |
| Clinical vertebral fracture (2) | 1.7 | 3.8 | 2.1 (0.5, 3.7) | 46 (8, 68) | 0.02 |
| Non-vertebral fracture (1) | 7.6 | 10.7 | 3.1 (0.3,5.9) | 27 (2,45) | 0.03 |
| Hip fracture | 2.0 | 3.5 | 1.5 (-0.1, 3.1) | 30 (-19, 59) | 0.18 |
- (1) Excluding finger, toe and facial fractures
- (2) Including clinical thoracic and clinical lumbar vertebral fractures
The incidence of first clinical fracture with zoledronic acid injection, represents a 35% reduction in the risk of clinical fractures over time for the zoledronic acid injection group versus the placebo group (Hazard ratio of 0.65 (95% CI: 0.50 to 0.84) (p = 0.0012)).
Figure 2: Kaplan-Meier curve of time to first clinical fracture – placebo-controlled study, Study 2310 (ITT population)
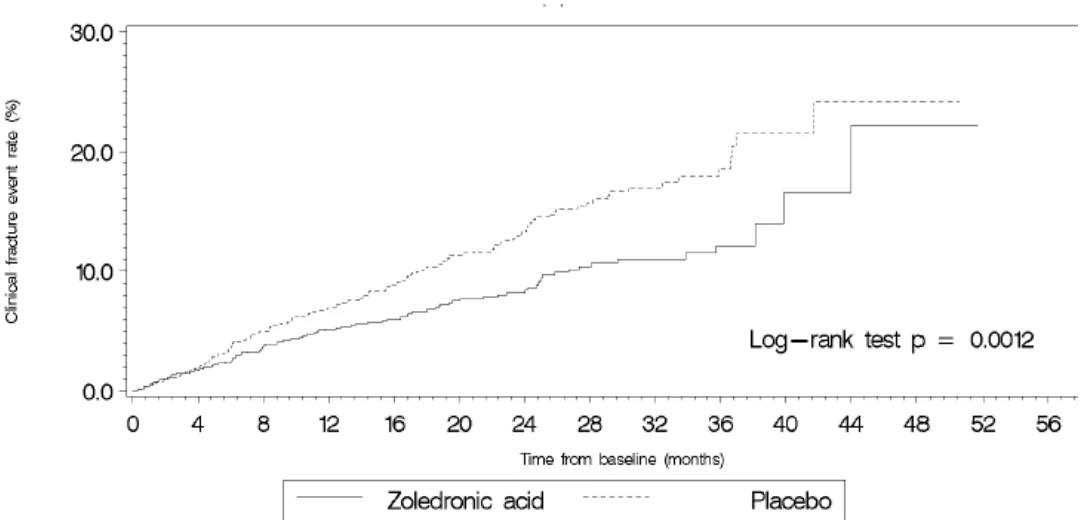
Effect on Bone Mineral Density (BMD) in the HORIZON-RFT study
Treatment with zoledronic acid injection resulted in significant increases of BMD measures for the total hip and femoral neck (5.4% increase at the total hip and 4.3% increase at the femoral neck over 24 months as compared to placebo).
Osteoporosis in men
Study demographics and trial design
The efficacy and safety of zoledronic acid injection in men with osteoporosis were assessed in a randomized, multicentre, double-blind, active-controlled study of 302 men aged 25-86 years (mean age of 64 years) and 95.4% Caucasian. The duration of the trial was two years. Patients were randomized to either zoledronic acid injection, which was administered once annually as a single 5 mg dose in 100 mL solution infused over 15 minutes for a total of two doses, or to oral alendronate 70 mg weekly for two years. All participants received 1000 mg elemental calcium plus 800 to 1000 IU vitamin D supplementation per day. Efficacy was demonstrated if non-inferiority to alendronate was shown with respect to the percentage change in lumbar spine BMD at 24 months relative to baseline.
Table 20: Summary of patient demographics for clinical trial in male osteoporosis
| Study # | Trial design | Dosage, route of administration and duration | Study subjects (N= population treated) | Mean age (Range) | Gender Male/Female (N=randomized patients) | |||||||||
| Zoledronic acid injection | alendronate | Zoledronic acid injection | alendronate | |||||||||||
| M2308 | One dose of 5 mg zoledronic acid injection /100 mL over 15 min (or placebo infusion) per 12 months Alendronate (or placebo) 70 mg once a week Duration: 24 months | N = 154 | N = 148 | 64.5 (25-85) | 63.5 (29-86) | 302 (100% male / 0% female) | ||||||||
Study results
Effect on Bone Mineral Density (BMD)
An annual infusion of zoledronic acid injection was non-inferior to weekly alendronate for the percentage change in lumbar spine BMD at month 24 relative to baseline (zoledronic acid injection 6.1% compared to alendronate 6.2%).
Glucocorticoid-induced osteoporosis
Study demographics and trial design
The efficacy and safety of zoledronic acid injection in the glucocorticoid-induced osteoporosis trial were assessed in a randomized, multicentre, double-blind, stratified (treatment and prevention), active- controlled study of 833 Caucasian (95.1%), men and women aged 18-85 years (mean age of 54.4 years) treated with ≥ 7.5 mg/day oral prednisone (or equivalent). Patients in the prevention subpopulation were treated with glucocorticoids ≤ 3 months prior to randomization, and those in the treatment subpopulation were treated with glucocorticoids > 3 months prior to randomization. The duration of the trial was one year. Patients were randomized to either zoledronic acid injection, which was administered once as a single 5 mg dose in 100 mL infused over 15 minutes, or to oral risedronate 5 mg daily for one year. All participants received 1000 mg elemental calcium plus 400 to 1000 IU vitamin D supplementation per day. The study was designed to show non-inferiority of a single infusion of zoledronic acid injection relative to risedronate in these two subpopulations. Efficacy was demonstrated if non-inferiority followed by superiority to risedronate was shown sequentially with respect to the percentage change in lumbar spine BMD at 12 months relative to baseline in the treatment and prevention subpopulations, respectively.
Table 21: Summary of patient demographics for clinical trial in Glucocorticoid-induced osteoporosis
| Study # | Trial design | Dosage, route of administration and duration | Study subjects (N= population treated) | Mean age (Range) | Gender Male/Female (N= randomized patients) | |||||
| Zoledronic acid injection | risedronate | Zoledronic acid injection | risedronate | |||||||
| O2306 | 1 dose of 5 mg zoledronic acid injection /100 mL over 15 min Risedronate 5 mg p.o./once daily Duration: 12 months | Treatment arm: N = 272 Prevention arm: N = 144 | Treatment arm: N = 273 Prevention arm: N = 144 | 54.3 (18-83) | 54.6 (19-84) | 833 zoledronic acid injection : (31.5% male/ 68.5% female) Risedronate: (32.1% male/ 67.9% female) | ||||
Study Results
Effect on Bone Mineral Density (BMD)
The increases in lumbar spine BMD at 12 months were significantly greater in the zoledronic acid injection-treated group compared to the risedronate group in both the treatment and prevention subpopulations. The results at this skeletal site were also statistically significant for the subgroup of men and postmenopausal women but were not significant for the subgroup of pre-menopausal women when analyzed separately for the treatment and the prevention subpopulations, although the study was not powered to determine significance in these subgroups.
Table 22: Effects of zoledronic acid injection and risedronate on bone mineral density of the lumbar spine
Population
Location
Zoledronic acid injection
n LS Mean (SE)
Risedronate
n LS Mean (SE)
LS Mean difference
(95% CI) 1
p-value
Treatment
Lumbar spine
All
249 4.06 (0.28)
245 2.71 (0.28)
1.36 (0.67, 2.05)
0.0001 men
75 4.69 (0.52)
77 3.27 (0.52)
1.42 (0.20,
2.64)
0.0232
Pre-menopausal women
63 3.12 (0.56)
60 1.74 (0.54)
1.38 (-0.08,
2.85)
0.0636
Postmenopausal women
111 3.68 (0.52)
108 2.31 (0.52)
1.37 (0.31,
2.43)
0.0118
Prevention
Lumbar spine
All
129 2.60 (0.45)
136 0.64 (0.46)
1.96 (1.04,
2.88)
<0.0001 men
38 2.46 (0.84)
40 -0.24 (0.90)
2.70 (0.99,
4.42)
0.0024
Pre-menopausal women
28 1.76 (0.75)
29 0.72 (0.72)
1.04 (-0.85,
2.92)
0.2746
Pre-menopausal women
63 3.25 (0.49)
67 1.32 (0.49)
1.92 (0.55,
3.29)
0.0063 n: number of patients
LS : Least Squares
SE: Standard Error
1 95% CI computed from three-way ANOVA model with treatment, geographical region, and gender (for all patients only) as factors
In both the treatment and prevention subpopulations, the increases in BMD at 12 months were significantly greater in the zoledronic acid injection-treated group compared to the risedronate group at the femoral neck, total hip, and trochanter (all p < 0.03). For the distal radius, the increases in BMD at 12 months were statistically significant for zoledronic acid injection compared to risedronate for the treatment subpopulation (p= 0.0223) but were not statistically significant for the prevention subpopulation (p= 0.278). A summary of the key results appear in Table 23.
Table 23: Effects of zoledronic acid injection and risedronate on bone mineral density of the total hip, femoral neck, trochanter and distal radius (modified ITT population), at 12 months
| Population | Location | Zoledronic acid n LS Mean (SE) | Risedronate n LS Mean (SE) | LS Mean difference (95% CI) 1 | p-value |
| Treatment | Total hip | 247 1.65 (0.21) | 239 0.45 (0.20) | 1.21 (0.71, 1.79) | <0.0001 |
| Femoral neck | 247 1.45 (0.31) | 239 0.39 (0.30) | 1.06 (0.32, 1.79) | 0.0050 | |
| Trochanter | 247 1.97 (0.31) | 239 0.63 (0.31) | 1.34 (0.59, 2.08) | 0.0005 | |
| Distal radius | 239 0.85 (0.27) | 237 0.09 (0.26) | 0.76 (0.11, 1.40) | 0.0223 | |
| Prevention | Total hip | 126 1.54 (0.36) | 135 0.03 (0.36) | 1.51 (0.78, 2.23) | <0.0001 |
| Femoral neck | 126 1.30 (0.45) | 135 -0.03 (0.46) | 1.33 (0.41, 2.25) | 0.0049 | |
| Trochanter | 126 2.75 (0.55) | 135 0.48 (0.56) | 2.27 (1.15, 3.39) | <0.0001 | |
| Distal radius | 128 0.06 (0.36) | 131 0.47 (0.38) | -0.42 (-1.17, 0.34) | 0.2784 |
n: number of patients
LS : Least Squares
SE: Standard Error
1 95% CI computed from three-way ANOVA model with treatment, geographical region, and gender as factors
Prevention of postmenopausal osteoporosis
Study demographics and trial design
The efficacy and safety of zoledronic acid injection in the prevention of osteoporosis in postmenopausal women were assessed in a 2-year randomized, multicenter, double-blind, placebo-controlled study of 581 postmenopausal women aged 45 years and older. Women were stratified by years since menopause into two strata; Stratum I women < 5 years from menopause (n=224) and Stratum II women > 5 years from menopause (n=357).
At the baseline visit, women in both Strata I and II were randomized to one of three treatment groups:
- Zoledronic acid injection 5 mg i.v. given as a single dose at randomization and placebo given at Month 12 (n=70 in Stratum I and n=111 in Stratum II)
- Zoledronic acid injection 5 mg i.v. given annually at randomization and at Month 12 (n=77 in Stratum I and n=121 in Stratum II)
- placebo given at randomization and at Month 12 (n=77 in Stratum I and n=125 in Stratum II)
Zoledronic acid injection was administered as a 5 mg dose in 100 mL solution infused over at least 15 minutes. All women received 500 to 1200 mg elemental calcium plus 400 to 800 IU vitamin D supplementation per day. The primary efficacy variable was the percent change of BMD at 24 Months relative to baseline. Women were Caucasian (94% in Stratum I and 92% in Stratum II) and had osteopenia (lumbar spine BMD T-score -1.0 to -2.5 and femoral neck BMD T-score greater than -2.5).
Table 24: Summary of patient demographics in the Prevention of postmenopausal osteoporosis study
| Study # | Trial design | Dosage, route of adminis- tration and duration | Study subjects | Mean age (Range) | Gender Male / Female (N=randomized patients) | |||||||||
| Zoledronic acid injection | Placebo | Zoledronic acid injection | Placebo | |||||||||||
| N2312 | Randomized, double-blind, stratified placebo- Controlled parallel group efficacy/safety study | Single dose of 5 mg zoledronic acid injection /100 mL over 15 min (or placebo infusion) per 12 months Duration: 24 months | Stratum I: ZOL 2x5mg N = 77 ZOL 1x5mg N = 70 Stratum II: ZOL 2x5mg N = 121 ZOL 1x5mg N = 111 | N = 202 Stratum I: N = 77 Stratum II: N = 125 | Stratum I: ZOL 2x5 mg 53.6 (46.0 –63.0) ZOL 1x5 mg 53.7 (46.0 –65.0) Stratum II: ZOL 2x5 mg 63.9 (46.0 –78.0) ZOL 1x5 mg 63.4 (47.0 –83.0) | Stratum I: 54.4 (45.0– 68.0) Stratum II: 64.2 (46.0-81.0) | 581 (0 % male/ 100% female) | |||||||
Study Results
Effect on Bone Mineral Density (BMD)
Zoledronic acid injection significantly increased lumbar spine BMD relative to placebo at Month 24 across both strata. Treatment with zoledronic acid injection given as a single dose at randomization (and placebo given at Month 12) resulted in 4.0% increase in BMD in Stratum I patients and 4.8% increase in Stratum II patients over 24 months. Placebo given at randomization and at Month 12 resulted in 2.2% decrease in BMD in Stratum I patients and 0.7% decrease in BMD in Stratum II patients over 24 months. Therefore, treatment with a single dose of zoledronic acid injection resulted in 6.3% increase in lumbar spine BMD in Stratum I patients and 5.4% increase in Stratum II patients over 24 months relative to placebo (both p<0.0001). Similar increases in lumbar spine BMD were observed in both Strata when zoledronic acid was administered annually. There was no significant difference seen in either Stratum for the percent increase from baseline in lumbar spine
BMD over 24 months relative to placebo when zoledronic acid was administered either as a single dose or annually.
Table 25: Between-treatment comparison for percentage change in lumbar spine BMD at Month 24 (LOCF) relative to baseline, by stratum (ITT population)
| Treatment | n | LSM | Pair-wise treatment comparison | LSM difference | 95% CI of difference (1) | p-value (2) |
| Stratum I | ||||||
| ZOL 1x5 mg | 70 | 4.03 | ZOL 1x5 mg - placebo | 6.27 | 5.15, 7.39 | <0.0001 |
| Placebo | 77 | -2.24 | ||||
| Stratum II | ||||||
| ZOL 1x5 mg | 111 | 4.76 | ZOL 1x5 mg - placebo | 5.41 | 4.46, 6.36 | <0.0001 |
| Placebo | 125 | -0.65 |
LSM = least squares mean, CI = confidence interval
Stratum I: women < 5 years from menopause, Stratum II: women ≥ 5 years from menopause
- (1) 95% confidence interval is calculated based on a t-distribution
- (2) p-value is obtained from ANOVA with treatment and pooled country as explanatory variables
Treatment with a single dose of zoledronic acid injection significantly increased BMD at 24 months relative to placebo at other bone sites including total hip, femoral neck, trochanter, and distal radius.
Table 26: Effects of zoledronic acid injection on bone mineral density of the total hip, femoral neck, trochanter, and distal radius (ITT population), at 24 months, by stratum, for zoledronic acid 5 mg vs. placebo
| Stratum | Location | Zoledronic acid injection n LS Mean (SE) | Placebo n LS Mean (SE) | LS Mean difference (95% CI) 1 | p-value |
| Stratum I | Total hip | 58 2.55 (0.317) | 71 -2.10 (0.293) | 4.65 (3.86, 5.43) | <0.0001 |
| Femoral neck | 58 2.01 (0.549) | 71 -1.55 (0.508) | 3.56 (2.20, 4.92) | <0.0001 | |
| Trochanter | 58 4.51 (0.449) | 71 -1.93 (0.415) | 6.44 (5.32, 7.55) | <0.0001 | |
| Distal radius | 57 -0.27 (0.424) | 71 -3.23 (0.384) | 2.96 (1.92, 4.00) | <0.0001 | |
| Stratum II | Total hip | 97 2.11 (0.282) | 115 -1.04 (0.265) | 3.16 (2.40, 3.91) | <0.0001 |
| Femoral neck | 97 1.46 (0.366) | 115 -1.18 (0.343) | 2.65 (1.67, 3.62) | <0.0001 | |
| Trochanter | 97 3.97 (0.372) | 115 -0.65 (0.348) | 4.62 (3.63, 5.61) | <0.0001 | |
| Distal radius | 96 -0.13 (0.336) | 112 -1.85 (0.317) | 1.72 (0.82, 2.61) | 0.0002 |
n: number of patients
LS : Least Squares
SE: Standard Error
1 95% CI computed from three-way ANOVA model with treatment, geographical region, and gender as factors
Paget’s disease of bone
Study demographics and trial design
Zoledronic acid injection 5 mg was studied in male (approximately 70%) and female (approximately 30%) patients aged above 30 years with primary mild to moderate Paget’s disease of the bone (median serum alkaline phosphatase level 2.6-3.0 times the upper limit of the age-specific normal reference range at the time of study entry). Diagnosis of Paget’s disease of bone was confirmed by radiographic evidence.
The efficacy of one infusion of zoledronic acid injection versus oral daily doses of 30 mg risedronate for 2 months was demonstrated in two, 6-month, double-blind, active-controlled comparative clinical trials. Therapeutic response was defined as either normalization of serum alkaline phosphatase (SAP) or a reduction of at least 75% from baseline in total SAP excess at the end of six months. SAP excess was defined as the difference between the measured level and midpoint of normal range. The normal laboratory reference range for SAP is 31-110 U/L for females and males between 20-58 years, and 35-115 U/L for females and males >58 years.
Table 27: Summary of patient demographics for clinical trials in Paget’s disease of bone
| Study # | Trial design | Dosage, route of administration and duration | Study subjects (N=population treated) | Mean age (Range) | Gender Male/Female n (%) | |||||
| Zoledronic acid injection | RIS | |||||||||
| 2304 | international, randomized, double-blind, safety and efficacy trials | One dose of 5 mg Zoledronic acid injection /100 mL over 15 min (or placebo infusion) or 30 mg oral risedronate o.d. for 2 months (or placebo capsules). Duration: 6 months | Zoledron ic acid injection: N = 89 RIS: N = 82 | 70.4 (42.0 – 94.0) | 72.1 (44.0 – 87.0) | Zoledronic acid injection: 62 (68.9) / 28 (31.1) RIS: 61 (74.4) / 21 (25.6) | ||||
≥65 years: 65 (72.2) | ≥65 years: 65 (79.3) | |||||||||
| 2305 | Zoledronic acid injection: N = 88 RIS: N = 90 | 71.3 (45.0 –92.0) | 68.2 (34.0 –88.0) | Zoledronic acid injection : 62 (67.4) / 30 (32.6) RIS: 57 (61.3) / 36 (38.7) | ||||||
≥65 years: 71 (77.2) | ≥65 years: 64 (68.8) | |||||||||
Study results
In both trials, zoledronic acid injection demonstrated a significantly greater and more rapid therapeutic response compared with the active comparator risedronate and returned more patients to normal levels of bone turnover, as evidenced by biochemical markers of bone formation (SAP, serum N- terminal propeptide of type I collagen (P1NP)) and bone resorption (serum CTx 1 (cross-linked C-telopeptides of type I collagen) and urine α-CTx). In the Paget’s trials, zoledronic acid injection reduced the bone markers to the normal laboratory reference ranges (see Table 28).
Table 28: Combined study results in the Paget’s disease of bone
| Primary Endpoints | Zoledronic acid injection 5mg | Risedronate 30mg | p-value |
| Primary efficacy variable | |||
| Proportion of therapeutic responders at 6 months | 96% (169/176) | 74% (127/171) | < 0.001 |
| SAP Normalization | 89% (156 /176) | 58% (99/171) | < 0.0001 |
| Secondary efficacy variables | |||
| Bone Turnover Markers | |||
| Comparison for log serum CTx ratio at Day 10 | 0.09 | 0.50 | < 0.001 |
| Comparison for log urine α-CTx ratio at Day 10 | 0.05 | 0.54 | < 0.001 |
| Comparison for log SAP ratio at Day 28 | 0.49 | 0.71 | < 0.001 |
| Responders | |||
| Proportion of subjects who achieved normalization at Day 28 | 7% (13/176) | 1% (1/170) | < 0.001 |
| Time to first therapeutic response (mean/median days) | 62.8/64 | 100.6/89 | < 0.001 |
At 6 months (182 days), combined data from both trials showed that 96.0% (169/176) of zoledronic acid injection-treated patients achieved a therapeutic response as compared with 74.3% (127/171) of patients treated with risedronate (p <0.001) (see Figure 3). In addition, at 6 months, 88.6% (156/176) of zoledronic acid injection-treated patients achieved remission (normalization of SAP levels) compared to 57.9% (99/171) of patients treated with risedronate (p<0.0001) (see Figure 4).
Figure 3 Therapeutic response
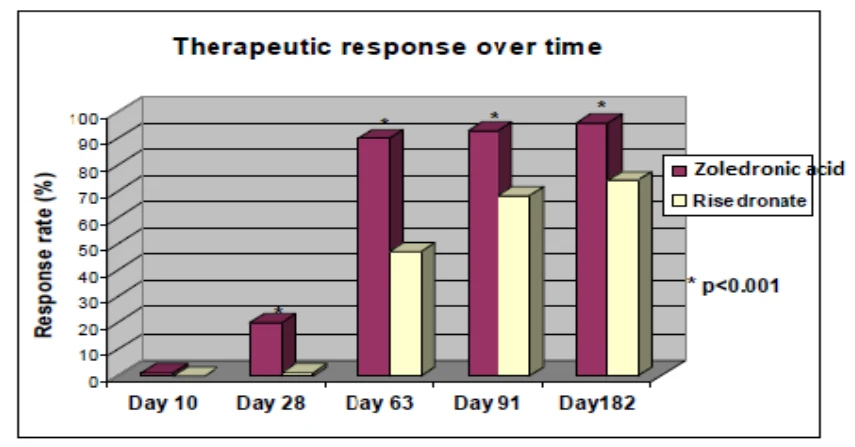
Therapeutic response over time:
Visit n/N (proportion): Day 10: zoledronic acid injection 2/165 (0.01); RIS 0/165 (0.00); Day 28: zoledronic acid injection 35/176 (0.20); RIS 2/170 (0.01); Day 63 zoledronic acid injection 158/176 (0.90) RIS 81/171 (0.47); Day 91 zoledronic acid injection 163/176 (0.93) RIS 116/171 (0.68); Day 182 zoledronic acid injection 169/176 (0.96) RIS 127/171 (0.74)
Figure 4 SAP normalization over time
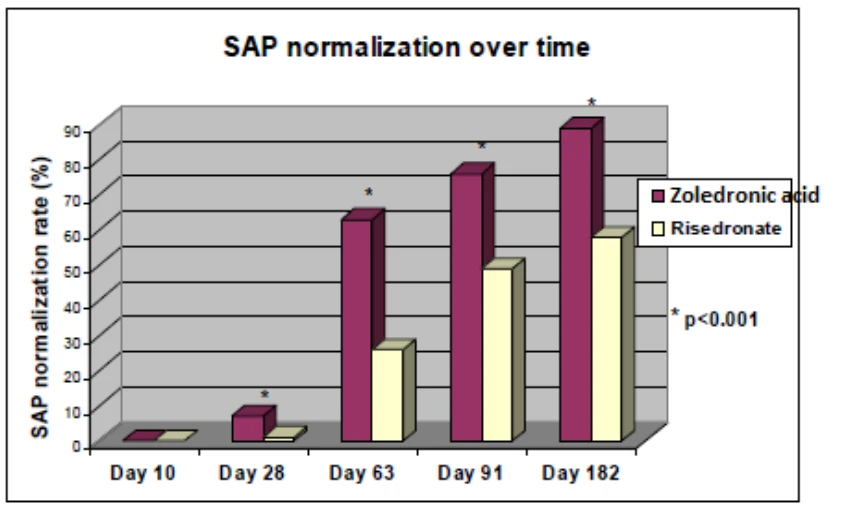
SAP normalization over time:
Visit n/N (proportion): Day 10: zoledronic acid injection 0/165 (0.00) RIS 0/165 (0.00); Day 28 : zoledronic acid injection 13/176 (0.07) RIS 1/170 (0.01); Day 63 zoledronic acid injection 111/176 (0.63) RIS 45/171 (0.26); Day 91 zoledronic acid injection 134/176 (0.76) RIS 83/171 (0.49); Day 182 zoledronic acid injection 156/176 (0.89) 99/171 (0.58)
Onset of action
Zoledronic acid injection treatment results in a more rapid treatment response than treatment with risedronate. The median time to therapeutic response was significantly faster (64 days) for zoledronic acid compared to risedronate-treated patients (89 days) (see Table 29).
Table 29: Time to first therapeutic response (Intent-to-treat patients)
| Treatment | Mean (median) days | N | Number of Responders | P-value (1) |
| Zoledronic acid injection | 62.8 (64) | 182 | 169 | <0.0001 |
| Risedronate | 106.6 (89) | 175 | 131 | --- |
A therapeutic response is defined as normalization of SAP or a reduction of ≥75% from baseline in SAP excess.
N is the number of patients
1 P-value is calculated from the Wald test of the Cox proportional hazards regression model.
Therapeutic response by disease factor
The therapeutic response to zoledronic acid was similar across all demographic and disease severity groups (gender, age, previous bisphosphonate use, and disease severity). At 6 months, in each of the baseline disease severity subgroups (baseline SAP <3xULN, 3xULN) the percentage of zoledronic acid injection-treated patients who achieved therapeutic response was 96.7% and 95.3% compared to risedronate-treated patients at 74.7% and 73.6%, respectively both at p <0.0001 (see Table 30).
In patients who had previously received treatment with oral bisphosphonates, a significantly greater therapeutic response was observed with zoledronic acid injection (96.4%) relative to risedronate (55.0%) (p< 0.0001). In patients naïve to previous treatment, a greater therapeutic response was also observed with zoledronic acid injection (97.6%) relative to risedronate (85.5%) (p =0.0075) (see Table 30).
Table 30: Proportion of patients who achieved therapeutic response at 6 months by disease factors
Subgroup
Zoledronic acid injection
n/N (Proportion)
Risedronate
n/N (Proportion)
p-value 1 for treatment difference
Baseline SAP
< 3xULN
87/90 (0.97)
74/99 (0.75)
<0.0001
≥ 3xULN
82/86 (0.95)
53/72 (0.74)
<0.0001
Last Paget’s therapy
Oral bisphos.
53/55 (0.96)
33/60 (0.55)
<0.0001
IV bisphos.
22/25 (0.88)
21/26 (0.81)
0.4590
Clodronate
6/6 (1.00)
2/2 (1.00)
NA
Others
8/8 (1.00)
6/7 (0.86)
0.2733
No previous therapy
80/82 (0.98)
65/76 (0.86)
0.0075
Symptomatic pain at screening
No
60/60 (1.00)
54/66 (0.82)
0.0006
Yes
109/116 (0.94)
73/105 (0.70)
<0.0001
SAP = serum alkaline phosphatase ULN = upper limit of normal
A therapeutic response is defined as normalization of SAP or a reduction of ≥ 75% from baseline in SAP excess
N=number of patients with baseline and at least one post-baseline SAP measurements
n = number of patients with therapeutic response at visit
1p-value is based on a Mantel-Haenszel test controlling for study for each category
The relative change in SAP at Day 28 (the third of seven secondary efficacy variables in the closed testing procedure) for the combined pivotal trials demonstrated a statistically significant reduction relative to baseline for zoledronic acid compared to risedronate (p < 0.001). The statistically significant reduction in SAP for zoledronic acid injection compared to risedronate was also demonstrated at Days 10, 63, 91, and 182 in the extended observation period.
Extended observation period
Paget’s disease of bone: Patients who were classified as responders at the end of the 6 month core study were eligible to enter an extended observation period. Since a larger population of zoledronic acid injection-treated patients achieved therapeutic response, a larger number of patients in the zoledronic acid injection group (N=153) entered the extended observation period compared to the risedronate group (N=115). After a mean duration of follow-up of 3.8 years from the initial time of dosing, the proportion of patients ending the Extended Observation Period due to the need for re-treatment (clinical judgment) was higher for risedronate (48 patients, or 41.7%) compared with zoledronic acid (11 patients, or 7.2%). The Kaplan-Meier model estimated mean time of ending the Extended Observation Period due to the need for Paget’s re-treatment from the initial dose was longer for zoledronic acid (7.7 years) than for risedronate (5.1 years).
The cumulative rate of maintaining therapeutic response in the extended follow-up period is displayed in Figure 5.
Six patients who achieved therapeutic response 6 months after treatment with zoledronic acid injection, and later experienced disease relapse during the extended follow-up period, were re-treated with zoledronic acid injection after a mean time of 6.5 years from initial treatment to re-treatment. Five of these six patients had SAP within the normal range at Month 6 (Last Observation Carried Forward, LOCF) (83.3%, 95% CI: 35.9%, 99.6%).
Figure 5 Cumulative rate of maintaining therapeutic response over time
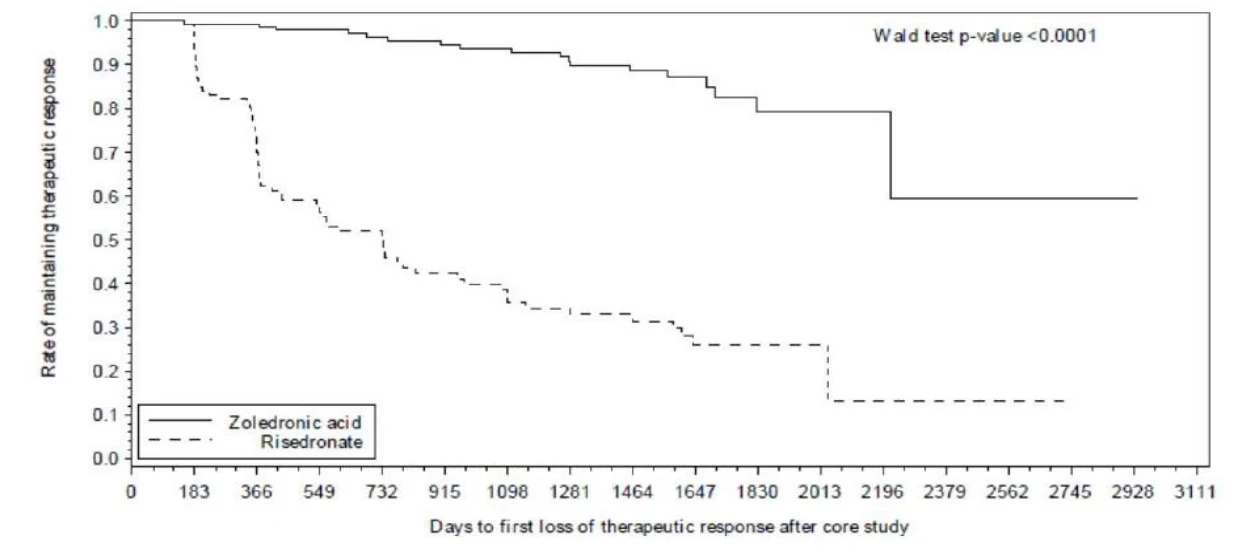
Time to first loss of therapeutic response: the occurrence of an SAP level that no longer meets the criteria of a therapeutic response (less than 75% reduction in SAP excess and/or SAP above the upper limit of the normal range)
DETAILED PHARMACOLOGY
Bone safety studies
Dose-response and duration of action of a single intravenous injection of zoledronic acid (0.8– 500 mcg/kg) were investigated in ovariectomized (OVX) adult rats for 8 months after dosing, which corresponds to approximately 8 remodeling cycles over 2.7 years in humans. A single dose of zoledronic acid protected against ovariectomy-induced bone loss; both the magnitude and duration of the effect were dose-dependent. The two highest doses of 100 and 500 mcg/kg significantly increased total bone mineral density, trabecular bone volume, trabecular number and connectivity density to levels above those of the sham-operated controls. Lower doses produced a weaker and less-prolonged effect. Mechanical testing at study termination showed a dose-dependent increase in bone strength to values above those of the sham-operated controls at the higher dose. Histomorphometric analysis and measurement of plasma osteocalcin levels confirmed that bone formation was present at 32 weeks post-injection even at the highest dose of 500 mcg/kg. This dose in rats is approximately 3.4 fold higher than the 5 mg dose administered to a 50 kg patient.
In addition, two studies were performed in OVX rats (12-months treatment with 0.3, 1.5 and 7.5 mcg/kg) and OVX rhesus monkeys (16-months treatment with 0.5, 2.5 and 12.5 mcg/kg) using once-a-week subcutaneous injections. Zoledronic acid treatment dose-dependently prevented all the OVX-induced changes in bone mineral density, bone mechanics and biochemical markers of bone metabolism in serum and urine. Often full efficacy was achieved with the intermediate dose, whereas the low dose had either no or only a slight effect. Drug treatment was well tolerated, there were no clinically meaningful adverse events in either species. Static and dynamic histomorphometric analysis of bones from both of these experiments indicated that zoledronic acid dose-dependently prevented the changes induced by OVX in both trabecular and haversian bone. Moreover, there was no indication of any abnormality in bone or marrow tissue, no evidence of a mineralizing defect, no accumulation of osteoid, and no woven bone. Except for its high anti-resorptive potency, the effect of zoledronic acid on bone was qualitatively similar to that published for other bisphosphonates. These results demonstrate bone safety in a laboratory rodent and a non-human primate species with a more frequent dosing regimen, and a 5-to-8 fold higher total yearly dose (based on 5 mg human dose), than the planned once a year dosing in humans. Overall, the results provide preclinical evidence for the efficacy and bone safety of zoledronic acid.
TOXICOLOGY
Acute Toxicity
Table 31: Acute Toxicology
| Species | Route | Doses (mg/kg) | Findings |
|---|---|---|---|
| Rat | i.v. | 0.6, 6, 30, 60, 80 | > 6 mg/kg: mortality and clinical signs 6 mg/kg: compound-related renal tubular lesions LD50 = approximately 13 mg/kg |
| Rat | i.v. | 1.6, 8, 16, 32 | > 8 mg/kg: mortality, clinical signs, necropsy findings in kidney, liver, GI tract ≥ 1.6 mg/kg: ↓ BW, FC, injection site irritation max. non lethal dose: 1.6 mg/kg min. lethal dose: 8 mg/kg |
| Dog | i.v. | 2,10 | 2 mg/kg: no clinical signs 10 mg/kg: clinical signs, mortality after 6 days, intestinal hemorrhage |
| Mouse | s.c. | 10,50 | 10 mg/kg: no clinical signs 50 mg/kg: mortality, clinical signs LD50= 10-50 mg/kg in males and > 10 mg/kg in females |
| Rat | p.o. | 200, 2000 | > 200 mg/kg: ↓ FC,BW, clinical signs, necropsy findings in stomach: enlarged, red lesions 2000 mg/kg: 100% mortality |
The acute parenteral toxicity of zoledronic acid was moderate to marked in the mouse, rat and dog, where the kidney was identified as a target organ.
Subacute and Chronic Toxicity
Table 32: Subacute and Chronic Toxicity
| Study Type | Species | Route | Doses (mg/kg) | Findings | ||||||||
|---|---|---|---|---|---|---|---|---|---|---|---|---|
| Study Type | Species | Route | Doses (mg/kg) | Findings | ||||||||
| Study Type | Species | Route | Doses (mg/kg) | Findings | ||||||||
| Intravenous | ||||||||||||
10-Day range-Finding | Rat | i.v. | 0.06, 0.6, 6 | 0.06 mg/kg: well tolerated 0.6 mg/kg: clin. signs; micro in kidneys, liver | ||||||||
| 6 mg/kg: sacrifice due to severe clin. signs; micro in bone, kidneys, stomach, liver, thymus, spleen, lymph nodes | ||||||||||||
| NOAEL: 0.06 mg/kg | ||||||||||||
| 2-Week | Rat | i.v. | 0.06, 0.6, 3.2 | > 0.06 mg/kg: local irritation, pharmacol bone changes | ||||||||
(every third day for 18 days) | > 0.6 mg/kg: gastric lesions | |||||||||||
| 3.2 mg/kg: mortality, clin signs; ↓ BW/FC, clin lab alterations, ↑ adrenal, kidney, liver wgts, nephropathy, hepatocellular hypertrophy | ||||||||||||
| NOAEL: not established | ||||||||||||
10-Day range- finding | Dog | i.v. | 0.1, 1 | > 0.1 mg/kg: micro in bone rib, injection sites 1 mg/kg: clin. signs; micro findings in stomach, intestine, liver, lung, thymus NOAEL: 0.1 mg/kg | ||||||||
4-Week + 1 mo. Recovery | Dog | i.v. | 0.02, 0.06, 0.2 | > 0.06 mg/kg: clinical signs 0.2 mg/kg: clin. signs; micro in GI tract NOAEL: 0.02 mg/kg | ||||||||
| 3-Month + 1 mo. Recovery | Dog | i.v. | 0.01 ,0.03, 0.1→0.2 | >0.01 mg/kg: genital tract atrophy (F); ↑ primary spongiosa in bone; splenic histiocytosis; lung inflammation, thymic atrophy > 0.03 mg/kg: moribund sacrifice at 0.1→0.2 mg/kg due to inj. site irritation, ↓ BW/FC, ↑ ALAT/ASAT, ↓ bone AP, PO4, creatinine and ↓ RBC indices; inj. site ulceration, kidney lesions, genital tract (M) & pancreatic atrophy, inflammation of urinary bladder, esophagus, stomach and liver. | ||||||||
| NOAEL: not established | ||||||||||||
| 26/52-wk+6 mo. Recovery | Dog | i.v. | 0.005, 0.03, 0.1 | All doses: inj site irritation; ↓ phosphate; pharmacol. bone changes >0.03 mg/kg : micro in kidneys, GI tract; ↓ BUN, ↑ total protein. 0.1 mg/kg: ↓ creatinine, ↑ ASAT, ↓Ca. NOAEL: 0.005 mg/kg | ||||||||
| Bone analyses (26/52-wk + 6 mo. Recovery) | Dog | i.v. | 0.005, 0.03, 0.1 | All biomechanical parameters assessing bone quality showed either no deleterious effect or an increase in quality at pharmacologically efficacious doses. | ||||||||
| Subcutaneous | ||||||||||||
| 10-Day range- finding | Rat | s.c. | 0.2, 0.6, 2 | 2 mg/kg: clin. signs; microscopic changes in kidneys, liver; spleen, thymus, lymph nodes, lung and adrenals.
≥0.2 mg/kg: Local irritation at the injection sites | ||||||||
| 1-Month + 1 mo recovery | Rat | s.c. | 0.02, 0.06, 0.2 | 0.2 mg/kg: swelling at injection site; clin. signs; micro findings in liver, lymph nodes ≥0.06 mg/kg: clin. signs; micro findings of spleen, injection sites, skeletal muscle; NOAEL: 0.02 mg/kg | ||||||||
| 3-Month + 1 mo recovery | Rat | s.c. | 0.01, 0.03, 0.1 | Tolerated without mortality at doses up to and including 0.1 mg/kg. Pharmacologic bone changes. NOAEL 0.01 mg/kg in females. No NOAEL in males due to reduced BW/FC at all doses. | ||||||||
| 6/12-Month + 6 mo recovery | Rat | s.c. | 0.001, 0.003, 0.01 | 0.001 mg/kg: ↓ bone AP, ↑ reticulocyte count, splenic hemosiderosis and congestion, ↑ splenic hematopoiesis, ↑ cellularity of femoral/tibial marrow, pharmacological bones changes. Following bone morphometry, no deleterious effects after administration for 12 months. 0.003 mg/kg: ↓ RBC parameters, ↑ fibrinogen, renal tubular changes, progressive nephropathy. 0.01 mg/kg: testicular tubular atrophy Bone morphometry on bone (tibia) did not reveal deleterious effects NOAEL: 0.001 mg/kg | ||||||||
| Oral | ||||||||||||
| 13-week | Mouse | p.o. | 0, 0.3, 3, 10, 30→20 | 0.3 – 30→20 mg/kg: mortality; respiratory signs; ↓ FC; pharmacologic bone changes 3 - 30→20 mg/kg: ↓BW; laryngeal, tracheal & bronchial inflammation | ||||||||
10-Day range-finding | Rat | p.o. | 1, 10, 100 | 1 and 10 mg/kg: well-tolerated 100 mg/kg: mortality & moribund sacrifice after 1 wk; clin. signs; gastritis, GI tract necrosis, acute renal tubular lesions, liver changes; lymphoid depletion spleen, thymus. | ||||||||
| 1-Month + 1 mo recov. | Rat | p.o. | 62060 | 6 mg/kg: well-tolerated >20 mg/kg: clin signs; liver, spleen, lymph nodes 60 mg/kg: mortality; GI tract, kidneys, salivary glands, thymus, adrenal, lung, trachea NOAEL: 6 mg/kg | ||||||||
| 6-Month +1 mo recov. | Rat | p.o. | 0.1, 1, 10 | >0.1 mg/kg: bone >1 mg/kg: clin signs 10 mg/kg: mortality NOAEL: 0.1 mg/kg | ||||||||
| 10-Day | Dog | p.o. | 1→30, 10 (for 9d); 30 (for 10d) | 1→30 mg/kg: clin. signs; micro findings in kidneys, esophagus, liver; pharmacol bone changes. 10 mg/kg: no significant findings | ||||||||
| 1-Month | Dog | p.o. | 3, 10, 30 | > 3 mg/kg: clin signs ≥ 10 mg/kg: mortality; liver, lung, thymus 30 mg/kg: gingiva, pancreas, adrenals | ||||||||
| 6-Month + 1 mo. Recov | Dog | p.o. | 0.01, 0.1, 1 | Well-tolerated at doses of up to 1 mg/kg. Histological bone changes were considered pharmacologic NOAEL: 1 mg/kg | ||||||||
a From day 9 of dosing: 30 mg/kg for an additional 10 days
Reproductive Toxicity Studies
Table 33: Reproductive Toxicity Studies
Study Type
Species
Route
Doses (mg/kg)
Findings
Segment I
Rat
s.c.
0.01, 0.03, 0.1.
≥ 0.01: maternal toxicity and severe effects on parturition such that the study was terminated on lactation day 7
Segment II range-finding
Rat
s.c.
0.2, 0.6, 2
≥ 0.2 mg/kg: irritation at injection site
≥0.6 mg/kg: ↓ maternal BW. 9/10 dams with total resorption (embryo/fetal death) of progeny; remaining dam w/ only 2 fetuses (one with cleft palate)
Segment II
Rat
s.c.
0.1, 0.2, 0.4
> 0.2 mg/kg: ↓ maternal BW; ↓ fetal wgt; anomalies of viscera and/or skeleton w/ wavy ribs & delay in skeletal maturation.
0.4 mg/kg: 9/24 dams with total resorption of fetuses; some fetuses with edema, cleft palate, short lower jaw, abnormal ossification
Segment II range-finding
(non- pregnant)
Rabbit
s.c.
0.2, 0.6, 2
0.6 or 0.2 mg/kg suitable doses for main study.
Segment II range-finding (pregnant)
Rabbit
s.c.
0.1, 0.2 ,0.4
0.2, 0.4 mg/kg: early termination due to severe clinical signs/toxicity
0.1 mg/kg: ↓ fetal wgt; no signs of abnormal fetal development.
Segment II
Rabbit
s.c.
0,01, 0.03, 0.1
Maternal toxicity at 0.01 mg/kg due to ↓ blood calcium.
No embryo/fetotoxicity or teratogenicity
Adverse maternal effects were associated with drug-induced hypocalcemia.
Carcinogenesis
Standard lifetime carcinogenicity bioassays were conducted in mice and rats. Mice were given oral doses of zoledronic acid of 0.1, 0.5, or 2.0 mg/kg/day. There was an increased incidence of Harderian gland adenomas in males and females in all treatment groups (at doses ≥0.002 times the anticipated human intravenous dose, based on a comparison of relative body surface areas). These increases were not considered to be related to zoledronic acid administration as their occurrence lacked a dose response and the incidences were within the historical control range for animals of this age and strain in the testing facility. Moreover, these neoplasms are not biologically relevant as the Harderian gland is a unique, highly specialized organ which is not present or known to have any correlate in the human. Rats were given oral doses of zoledronic acid of 0.1, 0.5, or 2.0 mg/kg/day. No increased incidence of tumors was observed.
| Table 34: | Carcinogenesis | |
| Species | Route Doses (mg/kg) | Findings |
| Mouse | p.o. 0.1, 0.3, 1.0 | ≥ 0.1 mg/kg: nonproliferative hyperostosis |
| ≥ 0.3 mg/kg: ↓ BW | ||
| Rat | p.o. 0.1, 0.5, 2.0 | ≥ 0.1 mg/kg: nonproliferative hyperostosis |
≥ 0.5 mg/kg: ↓ BW,FC 2.0 mg/kg: ↑ extramedullary hematopoiesis |
In oral carcinogenicity studies in rodents, zoledronic acid revealed no carcinogenic potential.
Mutagenesis
Zoledronic acid was not genotoxic in the Ames bacterial mutagenicity assay, in the Chinese hamster ovary cell assay, or in the Chinese hamster gene mutation assay, with or without metabolic activation. Zoledronic acid was not genotoxic in the in vivo rat micronucleus assay.
Table 35: Mutagenesis
| Study Type | Findings |
|---|---|
in vitro: Ames a, Ames b , Amesc Range: a5000 mcg/plate (-S9/+S9), b390 - 25000 mcg/plate, c1250 mcg/plate (-S9/+S9) | Negative |
| in vitro: Cytogenetics test on Chinese hamster cells Range: 9.7 – 1250 mcg/mL | Negative |
in vitro: Gene mutation test using V79 Chinese hamster cells Range: 2 – 15 mcg/mL | Negative |
in vivo: Micronucleus in rats Range: 2.6 – 10.4 mg/kg | Negative |
a Bacterial test systems (S. typhimurium), with/without metabolic activation.
bBatch control
cBacterial test system (S. typhimurium/ E. coli), with/without metabolic activation.
There was no evidence of mutagenicity for zoledronic acid in a battery of tests covering various endpoints of genotoxicity.
Impairment of Fertility:
Female rats were given daily subcutaneous doses of zoledronic acid of 0.01, 0.03, or 0.1 mg/kg beginning 15 days before mating and continuing through gestation. Effects observed in the high- dose group (equivalent to human systemic exposure following a 5 mg intravenous dose, based on AUC comparison) included inhibition of ovulation and a decrease in the number of pregnant rats. Effects observed in both the mid-dose group and high-dose group (0.3 to 1 times human systemic exposure following a 5 mg intravenous dose, based on AUC comparison) included an increase in pre-implantation losses and a decrease in the number of implantations and live fetuses.
REFERENCES
- 1. Arden-Cordone M, Siris E, Lyles K, et al., Antiresorptive effect of a single infusion of microgram quantities of zoledronate in Paget’s disease of bone. Calcif Tissue Int 1997; 60: 415-418.
- 2. Buckler H, Fraser W, Hosking D, et al., Single infusion of zoledronate in Paget’s disease of bone: a placebo-controlled, dose-ranging study. Bone 1999; 24 (S5): 81S-85S.
- 3. Garnero P, Gineyts E, Schaffer A, et al., Measurement of urinary excretion of nonisomerized and beta-isomerized forms of type I collagen breakdown products to monitor the effects of the biphosphonate zoledronate in Paget’s disease. Arthritis Rheum 1998; 41: 354-360.
- 4. Green JR, Müller K, Jaeggi KA. Preclinical Pharmacology of CGP 42-446, a new, potent, heterocyclic bisphosphonate compound. J Bone Miner Res 1994; 9: 745-751.
- 5. Green J, Seltenmeyer Y, Jaeggi K, Widler L, Renal tolerability profile of novel, potent bisphosphonates in two short-term rat models, Pharmacol Toxicol 1997; 80: 225-230.
- 6. Risser F, Pfister C, Degen P, An enzyme inhibition assay for the quantitative determination of the new bisphosphonate zoledronate in plasma. J Pharm Biomed Anal 1997; 15: 1877-1880.
- 7. Body JJ, Diel I, Bell R. Profiling the safety and tolerability of bisphosphonates. Semin Oncol. 2004 Oct;31(5 Suppl 10):73-8.
- 8. Reid IR, et al. Intravenous zoledronic acid in post menopausal women with low bone mineral density. N Engl J Med 2002; 346:653-661.
- 9. Hornby SB, Evans GP, Hornby SL, Pataki A, Glatt M, Green JR. Long-Term Zoledronic Acid Treatment Increases Bone Structure and Mechanical Strength of Long Bones of Ovariectomized Adult Rats. Calcif Tissue Int 2003; 72:519–527.
- 10. Reid IR, Miller P, Lyles K, Fraser W, Brown JP, Saidi Y, Mesenbrink P, Su G, Pak J, Zelenakas K, Luchi M, Richardson P, Hosking D. Comparison of a single infusion of zoledronic acid with risedronate for Paget's disease. N Engl J Med. 2005 Sep 1;353(9):898-908.
- 11. Rogers MJ. New insights into the molecular mechanism of action of bisphosphonates. Curr Pharmaceut Design 2003; 9 (32):2643-2658
- 12.
Dunford JE, Thompson K, Coxon FP, Luckman SP, Hahn FM, Poulter CD, Ebetino FH, Rojers MJ. Structure-Activity Relationships for inhibition of Farnesyl diphosphate
- synthase in vitro and inhibition of bone resorption in vivo by nitrogen-containing bisphosphonates. J Pharmacol Exper Ther 2001; 296(2):235-242.
- 13. Black DM, Delmas PD, Eastell R, Reid IR, Boonen S, Cauley JA,et al. Once-yearly zoledronic acid for treatment of postmenopausal osteoporosis (HORIZON Pivotal Fracture Trial). N Engl J Med. 2007; 356(18):1809-22.
- 14. Lyles KW, Colờn-Emeric CS, Magaziner JS, Adachi JD, Pieper CF, Mautalen C, et al. Zoledronic Acid and Clinical Fractures and Mortality after Hip Fracture. N Engl J Med. 2007;Sept 17, [Epub ahead of print].
- 15.
- 16. ACLASTA (zoledronic acid injection) Solution for intravenous infusion, 5 mg / 100 mL, control 269479, product monograph, Sandoz Canada Inc. (2022-12-09).