


Product Monograph - Zopiclone (Sivem Pharmaceuticals)
Recent Major Label Changes
| 7 Warnings and Precautions, General | 2025-06 |
|---|---|
| 7 Warnings and Precautions, Hematologic | 2026-07 |
Table of Contents
Certain sections or subsections that are not applicable at the time of the preparation of the most recent authorized product monograph are not listed.
Recent Major Label Changes .................................................................................................. 2
Table of Contents .................................................................................................................. 2
Part 1: Healthcare Professional Information........................................................................... 5
1 Indications ...................................................................................................................... 5
1.1 Pediatrics ........................................................................................................................ 5
1.2 Geriatrics ........................................................................................................................ 5
2 Contraindications............................................................................................................ 5
3 Serious Warnings and Precautions Box ............................................................................ 6
4 Dosage and Administration ............................................................................................. 7
4.1 Dosing Considerations .................................................................................................... 7
4.2 Recommended Dose and Dosage Adjustment............................................................... 8
4.4 Administration ................................................................................................................ 9
4.5 Missed Dose ................................................................................................................... 9
5 Overdose ........................................................................................................................ 9
6 Dosage Forms, Strengths, Composition, and Packaging.................................................. 10
7 Warnings and Precautions ............................................................................................ 10
General ................................................................................................................................... 10
Dependence, Tolerance and/or Abuse Liability .................................................................... 12
Driving and Operating Machinery ......................................................................................... 14
Falls and Fractures ................................................................................................................. 14
Hematologic ........................................................................................................................... 15
Hepatic/Biliary/Pancreatic ..................................................................................................... 15
Immune .................................................................................................................................. 15
Neurologic .............................................................................................................................. 15
Psychiatric .............................................................................................................................. 16
Reproductive Health: Female and Male Potential Fertility ................................................... 18
Respiratory ............................................................................................................................. 18
7.1 Special Populations ...................................................................................................... 18
7.1.1 Pregnancy ..................................................................................................................... 18
7.1.2 Breastfeeding ............................................................................................................... 19
7.1.3 Pediatrics ...................................................................................................................... 19
7.1.4 Geriatrics ...................................................................................................................... 19
8 Adverse Reactions ........................................................................................................ 20
8.1 Adverse Reaction Overview ......................................................................................... 20
8.2 Clinical Trial Adverse Reactions .................................................................................... 20
8.4 Abnormal Laboratory Findings: Hematologic, Clinical Chemistry and, Other Quantitative Data .................................................................................................................. 21
8.5 Post-Market Adverse Reactions ................................................................................... 21
9 Drug Interactions .......................................................................................................... 22
9.1 Serious Drug Interactions ............................................................................................. 22
9.2 Drug Interactions Overview ......................................................................................... 22
9.3 Drug-Behaviour Interactions ........................................................................................ 23
9.4 Drug-Drug Interactions ................................................................................................. 23
9.5 Drug-Food Interactions ................................................................................................ 24
9.6 Drug-Herb Interactions................................................................................................. 24
9.7 Drug-Laboratory Test Interactions ............................................................................... 24
10 Clinical Pharmacology ................................................................................................... 24
10.1 Mechanism of Action ................................................................................................... 24
10.2 Pharmacodynamics ...................................................................................................... 25
10.3 Pharmacokinetics ......................................................................................................... 27
11 Storage, Stability, and Disposal ..................................................................................... 29
12 Special Handling Instructions ........................................................................................ 29
Part 2: Scientific Information ............................................................................................... 30
13 Pharmaceutical Information .......................................................................................... 30
14 Clinical Trials ................................................................................................................. 30
14.1 Clinical Trials by Indication ........................................................................................... 30
14.2 Comparative Bioavailability Studies ............................................................................. 30
15 Microbiology ................................................................................................................ 31
16 Non-Clinical Toxicology ................................................................................................. 31
17 Supporting Product Monographs .................................................................................. 37
Patient Medication Information .......................................................................................... 38
Part 1: Healthcare Professional Information
1 Indications
ZOPICLONE (zopiclone tablets) is indicated for short-term (usually not exceeding 7 to 10 days) use for:
- treatment and symptomatic relief of insomnia characterized by difficulty in falling asleep
- frequent nocturnal awakenings and/or early morning awakenings
where disturbed sleep results in impaired daytime functioning (see 4.1 Dosing Considerations).
1.1 Pediatrics
Pediatrics (< 18 years of age): No data are available to Health Canada; therefore, Health Canada has not authorized an indication for pediatric use.
1.2 Geriatrics
Geriatrics (≥65 years of age): Evidence from clinical studies and experience suggests that use in the geriatric population is associated with differences in safety or effectiveness (see 4.1 Dosing Considerations, 4.2 Recommended Dose and Dosage Adjustments, 7.1.4 Geriatrics).
Long-term use of ZOPICLONE should be avoided, including in geriatric patients. Enhanced monitoring is recommended (see 7 Warnings and Precautions, Falls and Fractures; 4.1 Dosing Considerations).
2 Contraindications
ZOPICLONE (zopiclone tablets) is contraindicated in patients:
- With known hypersensitivity to this drug or to eszopiclone, or to any component in the formulation. For a complete listing, see 6 Dosage Forms, Strengths, Composition, and Packaging.
- With myasthenia gravis.
- With severe hepatic insufficiency.
- With severe impairment of respiratory function (e.g., significant sleep apnea syndrome).
- Who have previously experienced complex sleep behaviours after taking any non-benzodiazepine sedative-hypnotic (see 3 Serious Warnings and Precautions Box, Complex Sleep-Related Behaviours).
3 Serious Warnings and Precautions Box
Addiction, Abuse and Misuse The use of benzodiazepines, or other sedative-hypnotic drugs, such as ZOPICLONE, can lead to abuse, misuse, addiction, physical dependence and withdrawal reactions. Abuse and misuse can result in overdose or death, especially when benzodiazepines, or other sedative-hypnotic drugs, such as ZOPICLONE, are combined with other medicines, such as opioids, alcohol or illicit drugs.
Withdrawal Benzodiazepines, or other sedative-hypnotic drugs, such as ZOPICLONE, can produce severe or life-threatening withdrawal symptoms.
(see 7 Warnings and Precautions, Dependence, Tolerance and/or Abuse Liability) Risks from Concomitant Use with Opioids Concomitant use of ZOPICLONE and opioids may result in profound sedation, respiratory depression, coma and death (see 7 Warnings and Precautions, General, Concomitant Use with Opioids).
Complex sleep behaviours
|
|---|
4 Dosage and Administration
4.1 Dosing Considerations
- Sleep disturbance may be the presenting manifestation of a physical and/or psychiatric disorder. Consequently, a decision to initiate symptomatic treatment of insomnia should only be made after the patient has been carefully evaluated.
- The use of hypnotics should be restricted for insomnia where disturbed sleep results in impaired daytime functioning.
- Treatment with ZOPICLONE should usually not exceed 7 to 10 consecutive days. Use for more than 2 to 3 consecutive weeks requires complete re-evaluation of the patient. Prescriptions for ZOPICLONE should be written for short-term use (7 to 10 days) and it should not be prescribed in quantities exceeding a 1-month supply
ZOPICLONE should always be prescribed at the lowest effective dose for the shortest duration possible.
Discontinuation
- ZOPICLONE can produce withdrawal signs and symptoms or rebound phenomena following abrupt discontinuation or rapid dose reduction (see 3 Serious Warnings and Precautions Box, Withdrawal; 7 Warnings and Precautions, Dependence, Tolerance and/or Abuse Liability). Abrupt discontinuation should be avoided and treatment - even if only of short duration - should be terminated by gradually tapering the dosage schedule under close monitoring.
- Tapering should be tailored to the specific patient. Special attention should be given to patients with a history of seizure (see 7 Warnings and Precautions).
If a patient experiences withdrawal signs and symptoms, consider postponing the taper or raising the ZOPICLONE dose, to the previous dosage prior to proceeding with a gradual taper.
Geriatric
- Geriatric patients in particular may be more sensitive to ZOPICLONE (see 7 Warnings and Precautions, Falls and Fractures).
- Long-term use of ZOPICLONE should be avoided, including in geriatric patients. Enhanced monitoring is recommended.
- Lactose is a non-medicinal ingredient in ZOPICLONE. Patients with rare hereditary diseases of galactose intolerance (galactosemia or glucose-galactose malabsorption) should not take ZOPICLONE (see 6 Dosage Forms, Strengths, Composition, and Packaging).
4.2 Recommended Dose and Dosage Adjustment
Use the lowest effective dose of ZOPICLONE for the patient. ZOPICLONE should be taken in a single intake and not be re-administered during the same night.
The product should be taken just before retiring for the night.
Adult dose: The recommended initial dose is 3.75 mg (one-half of a 7.5 mg tablet). The dose can be increased to 5 mg and further to 7.5 mg if clinically indicated. In some patients, the higher doses result in zopiclone blood levels in the morning high enough to produce impairment of driving and other activities that require full alertness (see 7 Warnings and Precautions, CNS Depressant Effects and Next-Day Impairment).
The 7.5 mg dose should not be exceeded (see 7 Warnings and Precautions).
Geriatrics (≥ 65 years of age): In the elderly and/or debilitated patient an initial dose of 3.75 mg (one-half of a 7.5 mg tablet) at bedtime is recommended. The dose may be increased to a maximum of 5 mg if the starting dose does not offer adequate therapeutic effect.
Patients with impaired liver function: The recommended dose is 3.75 mg (one-half of a 7.5 mg tablet) depending on acceptability and efficacy. If clinically indicated, a 5 mg may be used with caution in appropriate cases.
ZOPICLONE is contraindicated in patients with severe hepatic insufficiency (see 2 Contraindications).
Patients with renal insufficiency: Although no accumulation of zopiclone or of its metabolites has been detected in cases of renal insufficiency, it is recommended that patients with impaired renal function should start treatment with 3.75 mg (one-half of a 7.5 mg tablet). If clinically indicated, a 5 mg may be used with caution in appropriate cases.
Patients with chronic respiratory insufficiency: The recommended dose is 3.75 mg (one-half of a 7.5 mg tablet) depending on acceptability and efficacy. Up to 7.5 mg may be used with caution in appropriate cases.
ZOPICLONE is contraindicated in patients with severe impairment of respiratory function, e.g., significant sleep apnea syndrome (see 2 Contraindications).
Use with potent CYP3A4 inhibitors: An initial dose of 3.75 mg (one-half of a 7.5 mg tablet) at bedtime is recommended (see 9 Drug Interactions). If clinically indicated, 5 mg may be used with caution in appropriate cases.
Use with CNS depressants: Dosage adjustment may be necessary when ZOPICLONE is combined with other CNS-depressants because of the potentially additive effects (see 9 Drug Interactions).
Pediatrics (< 18 years of age): ZOPICLONE is not indicated for patients under 18 years of age.
4.4 Administration
Tablets are for oral administration. The 7.5 mg tablet can be broken into two equal parts of 3.75 mg.
4.5 Missed Dose
Patients should be instructed to take ZOPICLONE at bedtime just before retiring for the night. Patients who miss a dose should wait to take the next dose at the regular time. The missed dose must be skipped to avoid taking a double dose.
5 Overdose
Signs and Symptoms: Overdose is usually manifested by varying degrees of central nervous system depression ranging from drowsiness to coma according to the quantity ingested. In mild cases, symptoms include drowsiness, confusion, and lethargy; in more severe cases, symptoms may include ataxia, hypotonia, hypotension, methemoglobinemia, hemolysis/hemolytic anemia, respiratory depression, and coma. Overdose should not be life threatening unless combined with other CNS depressants, including alcohol. Other risk factors, such as the presence of concomitant illness and the debilitated state of the patient, may contribute to the severity of symptoms and very rarely can result in fatal outcome.
In voluntary or accidental cases of zopiclone tablets overdosage involving doses up to 340 mg, the principal effects reported were prolonged sleep, drowsiness, lethargy and ataxia.
Recommended Treatment: Symptomatic and supportive treatment in adequate clinical environment is recommended, attention should be paid to respiratory and cardiovascular functions. Activated charcoal is only useful when performed soon after ingestion.
Hemodialysis is of no value due to the large volume of distribution of zopiclone tablets. Flumazenil may be a useful antidote; however, flumazenil administration may contribute to the appearance of neurological symptoms (agitation, anxiety, convulsions and emotional lability). Intravenous fluids should be administered as needed.
As with the management of all overdosage, the possibility of multiple drug ingestion should be considered.
| For the most recent information in the management of a suspected drug overdose, contact your regional poison control centre or Health Canada's toll-free number, 1-844 POISON-X (1-844-764-7669). |
|---|
6 Dosage Forms, Strengths, Composition, and Packaging
Table – Dosage Forms, Strengths, and Composition
| Route of Administration | Dosage Form/ Strength/Composition | Non-Medicinal Ingredients |
|---|---|---|
| Oral | Tablet, 5 mg | Carnauba wax, hydroxypropyl methylcellulose, lactose monohydrate, magnesium stearate, microcrystalline cellulose, polyethylene glycol and titanium dioxide. |
| Oral | Tablet, 7.5 mg | Carnauba wax, D&C yellow #10, FD&C blue #1, hydroxypropyl methylcellulose, lactose monohydrate, magnesium stearate, microcrystalline cellulose, polyethylene glycol, and titanium dioxide. |
ZOPICLONE 5 mg:
Each round, white, biconvex film-coated tablet engraved APO on one side, ZOP over 5 on other and contains zopiclone 5 mg.
Available in bottles of 100 tablets.
ZOPICLONE 7.5 mg:
Each oval, blue, biconvex, film-coated, scored tablet engraved ‘APO 7.5’ on one side contains zopiclone 7.5 mg.
Available in bottles of 100 and 500 tablets.
7 Warnings and Precautions
General
The cause of insomnia should be identified wherever possible, and the underlying factors treated before a hypnotic is prescribed. The failure of insomnia to remit after 7 to 10 days of treatment may indicate the presence of a primary psychiatric and/or medical illness or the presence of sleep state misperception.
Worsening of insomnia or the emergence of new abnormalities of thinking or behaviour may be the consequence of an unrecognized psychiatric or physical disorder. These have also been reported to occur in association with the use of drugs that act at the benzodiazepine receptors.
Drug facilitated illicit use for criminal intent (Chemical Subjugation): Chemical subjugation refers to the administration of a psychoactive substance to a person without their knowledge to cause harm. It encompasses the reported illicit behaviours of Chemical Submission, Drug-Facilitated Crime, and Drug Facilitated Sexual Assault (DFSA).
The rapid onset of sedation, coupled with the amnestic features of ZOPICLONE, particularly when combined with alcohol, and administered without knowledge of the victim, induces incapacitation and thus facilitates criminal actions, such as sexual assault, theft, homicide, and other criminal transgressions.
Healthcare Providers should remain vigilant to the risk of Chemical Subjugation with ZOPICLONE and prescribe ZOPICLONE strictly according to the clinical evaluation of the patient’s medical need and ability to avoid diversion.
Concomitant Use with Opioids: Concomitant use of ZOPICLONE and opioids may result in profound sedation, respiratory depression, coma, and death. Because of these risks, reserve concomitant prescribing of these drugs for use in patients for whom alternative treatment options are not possible (see 3 Serious Warnings and Precautions Box, Risks from Concomitant Use with Opioids; 9 Drug Interactions, Serious Drug Interactions).
Observational studies have demonstrated that concomitant use of opioid analgesics and benzodiazepines increases the risk of drug-related mortality compared to use of opioid analgesics alone. Because of similar pharmacological properties, it is reasonable to expect similar risk with the concomitant use of other CNS depressant drugs, such as ZOPICLONE, with opioids.
If a decision is made to prescribe ZOPICLONE concomitantly with opioids, prescribe the lowest effective dosages and minimum durations of concomitant use. In patients already receiving an opioid analgesic, prescribe a lower initial dose of ZOPICLONE than indicated, and titrate based on clinical response. If an opioid analgesic is initiated in a patient already taking ZOPICLONE, prescribe a lower initial dose of the opioid analgesic and titrate based on clinical response. Follow patients closely for signs and symptoms of respiratory depression and sedation (see 5 Overdose).
Advise both patients and caregivers about the risks of respiratory depression and sedation when ZOPICLONE is used with opioids.
Advise patients not to drive or operate heavy machinery until the effects of concomitant use of the opioid have been determined (see 7 Warnings and Precautions, Driving and Operating Machinery).
Dependence, Tolerance and/or Abuse Liability
Use of benzodiazepines or other sedative-hypnotic drugs, such as ZOPICLONE, can lead to abuse, misuse, addiction, physical dependence (including tolerance) and withdrawal reactions. Abuse and misuse can result in overdose or death, especially when benzodiazepines, or other sedative-hypnotic drugs, such as ZOPICLONE, are combined with other medicines, such as opioids, alcohol, or illicit drugs.
The risk of dependence increases with higher doses and longer term use but can occur with short-term use at recommended therapeutic doses. Cases of dependence have been reported more frequently in patients treated with zopiclone tablets for longer than 4 weeks. The risk of dependence is greater in patients with a history of psychiatric disorders and/or substance (including alcohol) use disorder. Interdose daytime anxiety and rebound anxiety may increase the risk of dependency in ZOPICLONE treated patients.
- Discuss the risks of treatment with ZOPICLONE with the patient, considering alternative (including non-drug) treatment options.
- Carefully evaluate each patient’s risk of abuse, misuse and addiction, considering their medical condition and concomitant drug use, prior to prescribing ZOPICLONE. In individuals prone to substance use disorder, ZOPICLONE should only be administered if deemed medically necessary, employing extreme caution and close supervision.
- ZOPICLONE should always be prescribed at the lowest effective dose for the shortest duration possible.
- All patients receiving benzodiazepines or other sedative-hypnotic drugs, such as ZOPICLONE, should be routinely monitored for signs and symptoms of misuse and abuse. If a substance use disorder is suspected, evaluate the patient and refer them for substance abuse treatment, as appropriate.
Once physical dependence has developed, abrupt termination of treatment will be accompanied by withdrawal symptoms.
Withdrawal: Benzodiazepines or other sedative-hypnotic drugs, such as ZOPICLONE, can produce withdrawal signs and symptoms, ranging from mild to severe and even life threatening, following abrupt discontinuation or rapid dose reduction. The risk of withdrawal is higher with higher dosages and/or prolonged use, but can occur with short-term use at recommended therapeutic doses. Patients given therapeutic dosages for as few as 1 to 2 weeks can also have withdrawal symptoms including daytime anxiety between nightly doses.
Since symptoms of withdrawal are often similar to those for which the patient is being treated, it may be difficult to distinguish from a relapse of the patient’s condition.
Severe or life-threatening signs and symptoms of withdrawal include delirium, derealisation, depersonalisation, hallucinations, hyperacusis, seizures (including status epilepticus). (See 8.2 Clinical Trial Adverse Reactions, Withdrawal Symptoms).
Other withdrawal signs and symptoms, similar in character to those noted with barbiturates and alcohol, include abdominal and muscle cramps, cognitive impairment, convulsions, diarrhea, dysphoria, extreme anxiety, headache, hypersensitivity to light, noise and physical contact, insomnia, irritability, muscle pain or stiffness, paresthesia, perceptual disturbances, restlessness, sweating, tension, tremors and vomiting. There is also a possibility of rebound anxiety or rebound insomnia.
- Abrupt discontinuation should be avoided and treatment - even if only of short duration - should be terminated by gradually tapering the dosage schedule under close monitoring.
- Tapering should be tailored to the specific patient. Special attention should be given to patients with a history of seizure.
- If a patient experiences withdrawal symptoms, consider postponing the taper or raising the ZOPICLONE dose to the previous dosage prior to proceeding with a gradual taper.
- Inform patients of risk of discontinuing abruptly, reducing dosage rapidly or switching medications.
- As with all hypnotics, repeat prescriptions should be limited to those who are under medical supervision.
- Stress the importance of consulting with their health care professional in order to discontinue safely.
- It may be useful to inform the patient when treatment is started that it will be of limited duration and to explain precisely how the dosage will be progressively decreased.
- Patients experiencing withdrawal symptoms should seek immediate medical attention.
(see 3 Serious Warnings and Precautions Box, Addiction, Abuse and Misuse, Withdrawal; 4 Dosage and Administration, Dosing Considerations)
Rebound insomnia: A transient syndrome, whereby the symptoms that led to treatment with a sedative/hypnotic agent may recur in an enhanced form, upon treatment withdrawal. It may be accompanied by other reactions, including mood changes, anxiety and restlessness.
Since the risk of such phenomena is greater after abrupt discontinuation of ZOPICLONE, especially after prolonged treatment, it is, therefore recommended to decrease the dosage gradually and to advise the patient accordingly (see 8 Adverse Reactions). It is important that the patient should be aware of the possibility of rebound phenomena, thereby minimizing anxiety over such symptoms should they occur while the medicinal product is being discontinued.
Driving and Operating Machinery
CNS Depressant Effects and Next-Day Impairment: Like other sedative/hypnotic drugs, ZOPICLONE has CNS-depressant effects. Due to the rapid onset of action, ZOPICLONE should be ingested immediately prior to going to bed.
Patients should be cautioned against engaging in hazardous occupations requiring complete mental alertness or motor coordination such as operating machinery or driving a motor vehicle after ingesting the drug.
This includes potential impairment of the performance of such activities that may occur the day following ingestion of ZOPICLONE. The risk of next day psychomotor impairment, including impaired driving, is increased if ZOPICLONE is taken with less than a full night of sleep remaining; if a higher dose than the recommended dose is taken; if co-administered with other CNS depressants or drugs that increase the blood level of zopiclone. Patients should be cautioned against taking ZOPICLONE in these circumstances.
ZOPICLONE is not to be taken with alcohol or other sedative hypnotics (including other zopiclone products) at bedtime or the middle of the night. If concomitant use of another CNS depressant or a drug that increases zopiclone blood levels is clinically warranted, dosage adjustments of ZOPICLONE may be necessary.
Even if ZOPICLONE is taken as instructed, some patients may still have zopiclone blood levels in the morning high enough to produce impairment (see 4 Dosage and Administration and 9 Drug Interactions).
Patient counseling information regarding next-day impairment: Tell patients that ZOPICLONE has the potential to cause next-day impairment, and that this risk is increased if dosing instructions are not carefully followed. Tell patients not to drive a car or engage in hazardous activities requiring complete alertness until they experience how the drug affects them the next day. Tell patients that if they took ZOPICLONE as instructed and do not feel drowsy in the morning, they still have to wait for at least 12 hours after dosing before driving or engaging in other activities requiring full mental alertness, especially for elderly patients and for patients who take the 7.5 mg dose. Inform patients that impairment can be present despite feeling fully awake.
Falls and Fractures
There have been reports of falls and fractures among users of benzodiazepines or other sedative-hypnotic drugs, such as ZOPICLONE, due to adverse reactions such as sedation, dizziness and ataxia. The risk is increased in those taking concomitant sedatives (including alcoholic beverages), geriatric or debilitated patients.
Hematologic
Hemolysis/hemolytic anemia have been reported in cases of ZOPICLONE overdose (see 5 Overdose).
Hepatic/Biliary/Pancreatic
Patients with specific conditions: ZOPICLONE should be given with caution to patients with impaired hepatic or renal function. Dosage adjustments are recommended (see 4 Dosage and Administration, Recommended Dose and Dosage Adjustment).
ZOPICLONE is contraindicated in patients with severe hepatic insufficiency (see 2 Contraindications).
Immune
Severe Anaphylactic and Anaphylactoid Reactions: Rare cases of angioedema involving the tongue, glottis or larynx have been reported in patients after taking the first or subsequent doses of sedative-hypnotics, including zopiclone tablets. Some patients have had additional symptoms such as dyspnea, throat closing or nausea and vomiting that suggest anaphylaxis. Some patients have required medical therapy in the emergency department. If angioedema involves the throat, glottis or larynx, airway obstruction may occur and be fatal. Patients who develop angioedema after treatment with ZOPICLONE should not be rechallenged with the drug.
Patients with specific conditions: ZOPICLONE is contraindicated in patients with myasthenia gravis (see 2 Contraindications).
Lactose
Lactose is a non-medicinal ingredient in ZOPICLONE. Patients with rare hereditary diseases of galactose intolerance (galactosemia or glucose-galactose malabsorption) should not take ZOPICLONE (see 4 Dosage and Administration and 6 Dosage Forms, Strengths, Composition, and Packaging).
Neurologic
Abnormal thinking and behavioural changes: Abnormal thinking and other behavioural changes have been reported to occur in association with the use of benzodiazepines and benzodiazepine-like agents including zopiclone tablets, although rarely (see 8 Adverse Reactions). Some of the changes may be characterized by decreased inhibition, e.g., aggression or extroversion that seems excessive, similar to that seen with alcohol and other CNS depressants (e.g., sedative/hypnotics). Particular caution is warranted in patients with a history of violent behaviour and a history of unusual reactions to sedatives including alcohol and the benzodiazepines or benzodiazepine-like agents. Psychotic behavioural changes that have been reported include abnormal behaviour, restlessness, agitation, irritability, hallucinations, delusion, anger, nightmares,
delirium and depersonalization. Abnormal behaviours associated with the use of benzodiazepines or benzodiazepine-like agents have been reported more with chronic use and/or high doses but they may occur during the acute, maintenance or withdrawal phases of treatment.
It can rarely be determined with certainty whether a particular instance of abnormal behaviours listed above is drug induced, spontaneous in origin, or a result of an underlying psychiatric disorder. Nevertheless, the emergence of any new behavioural sign or symptom of concern requires careful and immediate evaluation. Should these occur, use of the product should be discontinued. These reactions are more likely to occur in the elderly.
Amnesia: Anterograde amnesia of varying severity has been reported following therapeutic doses of benzodiazepines or benzodiazepine-like agents. The event is rare with zopiclone tablets. Anterograde amnesia may occur, especially when sleep is interrupted or when retiring to bed is delayed after the intake of the tablet. Anterograde amnesia is a dose-related phenomenon and elderly subjects may be at particular risk.
Cases of transient global amnesia and “traveler’s amnesia” have also been reported in association with benzodiazepines, the latter in individuals who have taken the drug, often in the middle of the night, to induce sleep while travelling. Transient global amnesia and traveler’s amnesia are unpredictable and not necessarily dose-related phenomena.
To reduce the possibility of anterograde amnesia, patients should ensure that they take the tablet strictly when retiring for the night. Patients should be warned not to take ZOPICLONE under circumstances in which a full night’s sleep and clearance of the drug from the body are not possible before they need again to resume full activity.
Cognitive Function: The benzodiazepines and benzodiazepine-like agents affect mental efficiency, e.g., concentration, attention and vigilance. The risk of confusion is greater in the elderly and in patients with cerebral impairment.
Psychiatric
Anxiety, restlessness: An increase in daytime anxiety and/or restlessness has been observed during treatment with zopiclone tablets. This may be a manifestation of interdose withdrawal, due to the short elimination half-life of the drug.
Complex Sleep Behaviours: Complex sleep behaviours, including sleep-walking, sleep-driving and engaging in other activities while not fully awake, have been reported in patients who have taken zopiclone tablets. These behaviours may occur following the first or any subsequent use of ZOPICLONE. Patients can be seriously injured or injure others during complex sleep behaviours. Such injuries may be fatal. Other complex sleep behaviours (e.g., preparing and eating food, making phone calls, or having sex) have also been reported. Patients usually do not remember these events. Postmarketing reports have shown that complex sleep behaviours may occur with
ZOPICLONE at recommended doses, with or without the concomitant use of alcohol or other central nervous system (CNS) depressants (see 9 Drug Interactions). Discontinue ZOPICLONE immediately if a patient experiences a complex sleep behaviour (see 2 Contraindications).
ZOPICLONE is not to be taken with alcohol.
Caution is needed with concomitant use of other CNS depressants drugs as this appears to increase the risk of complex sleep behaviours.
Caution is recommended in patients with a personal or family history of sleepwalking. Although complex sleep behaviours have been reported in patients with or without history of sleepwalking, it is possible that some predisposed patients are at increased risk of experiencing these complex behaviours during treatment with ZOPICLONE.
The use of ZOPICLONE in patients with other disorders known to affect sleep and induce frequent awakenings (e.g. sleep apnea, Periodic Limb Movement Disorder, Restless Legs Syndrome) is discouraged, as they may be also at increased risk of complex sleep behaviours.
Treatment with ZOPICLONE is limited to a short duration (see 1 Indications, 4 Dosage and Administration).
Patients should be instructed not to exceed the maximum recommended dose as this appears to increase the risk of complex sleep behaviours.
Caution should be exercised with concomitant use of potent CYP3A4 inhibitors (see 9 Drug Interactions).
Due to the risk to the patient and the community, discontinuation of ZOPICLONE should be strongly considered for patients who report any such complex sleep behaviours.
Depression: Caution should be exercised if ZOPICLONE is prescribed to patients with signs and symptoms of depression that could be intensified by hypnotic drugs. The potential for self-harm (e.g., intentional overdose) is high in patients with depression and thus, the least amount of drug that is feasible should be available to them at any one time.
As with other hypnotics, ZOPICLONE does not constitute a treatment of depression and may even mask its symptoms.
Suicidality and Depression: Several epidemiological studies show an increased incidence of suicide and suicide attempt in patients with or without depression, treated with benzodiazepines and other hypnotics, including zopiclone. A causal relationship has not been established.
As with other sedative-hypnotic drugs, ZOPICLONE should be administered with caution in patients exhibiting symptoms of depression. Suicidal tendencies may be present, therefore the lowest possible quantity of ZOPICLONE should be supplied to these patients to reduce the risk of intentional overdosage by the patient. Since insomnia may be a symptom of depression, the patient should be re-evaluated if insomnia persists. In these patients, more direct monitoring of suicidal thinking may be warranted.
Paradoxical Reactions: Reactions like restlessness, aggravated insomnia, agitation, irritability, aggressiveness, delusion, rages, nightmares, parasomnia, depersonalization, hallucinations, psychoses, inappropriate behaviour, and other adverse behavioural effects are known to occur when using benzodiazepines or benzodiazepine-like agents. ZOPICLONE should be used with caution in patients who in the past manifested paradoxical reactions to alcohol and/or sedative medications.
Reproductive Health: Female and Male Potential Fertility
- Fertility: Animal data indicate possible effects on fertility at supratherapeutic doses (see 16 Non-Clinical Toxicology).
Respiratory
ZOPICLONE should be given with caution to patients with chronic pulmonary insufficiency. Dosage adjustments are recommended (see 4 Dosage and Administration). Respiratory depression has been reported in patients with compromised respiratory function. As hypnotics have the capacity to depress respiratory drive, precautions should be observed if ZOPICLONE is prescribed to patients with compromised respiratory function.
ZOPICLONE is contraindicated in patients with severe impairment of respiratory function, e.g., significant sleep apnea syndrome (see 2 Contraindications).
7.1 Special Populations
7.1.1 Pregnancy
The use of ZOPICLONE during pregnancy is not recommended.
If ZOPICLONE is prescribed to a woman of child-bearing potential, the patient should be warned of the potential risk to a fetus and advised to consult her physician regarding the discontinuation of the drug if she intends to become pregnant or suspects that she is pregnant.
Zopiclone crosses the placenta.
Benzodiazepines may cause fetal damage when administered during pregnancy. During the first trimester of pregnancy, several studies have suggested an increased risk of congenital malformations associated with the use of benzodiazepines. In certain epidemiological case-control studies, an increased incidence of cleft lip and palate was observed with benzodiazepines.
During the last weeks of pregnancy or during labor, ingestion of therapeutic doses of benzodiazepine hypnotic drugs has resulted in neonatal CNS depression due to transplacental distribution. Similar effects can be expected to occur with zopiclone, due to its pharmacological effects. Cases of reduced fetal movement and fetal heart rate variability have been described after administration of benzodiazepines during the second and/or third trimester of pregnancy.
Administration of zopiclone tablets during the late phase of pregnancy or during labor has been associated with effects on the neonate, such as hypothermia, hypotonia, feeding difficulties (which may result in poor weight gain) and respiratory depression.
A child born to a mother who took sedative/hypnotics agents chronically during the latter stages of pregnancy may have developed physical dependence and may be at risk for developing withdrawal symptoms in the postnatal period. Appropriate monitoring of the newborn in the postnatal period is recommended.
7.1.2 Breastfeeding
Zopiclone is excreted in human milk, and its concentration may reach 50% of the plasma levels. Insufficient data are available on zopiclone tablets to assess its safety during lactation. Therefore, the administration of ZOPICLONE to nursing mothers is not recommended.
7.1.3 Pediatrics
Pediatrics (< 18 years of age): The safety and efficacy of zopiclone tablets in children and young adults below the age of 18 have not been established. ZOPICLONE should not be prescribed in pediatric patients.
7.1.4 Geriatrics
Geriatrics (≥ 65 years of age): Elderly patients are especially susceptible to dose-related adverse effects, such as drowsiness, dizziness, or impaired coordination. Inappropriate, heavy sedation may result in accidental events/fall. Therefore, the ZOPICLONE dose in elderly patients should not exceed 5 mg (see 4 Dosage and Administration, 1.2 Geriatrics). Anterograde amnesia is a dose-related phenomenon and elderly subjects may be at particular risk.
Long-term use of ZOPICLONE should be avoided, including in geriatric patients or debilitated patients who may be more sensitive to ZOPICLONE. There is an increased risk of cognitive impairment, delirium, falls, fractures, hospitalizations and motor vehicle accidents in these users. Enhanced monitoring is recommended in this population.
8 Adverse Reactions
8.1 Adverse Reaction Overview
The most common adverse reaction seen with zopiclone tablets is taste alteration (bitter taste). Severe drowsiness and/or impaired coordination are signs of drug intolerance or excessive doses.
8.2 Clinical Trial Adverse Reactions
Clinical trials are conducted under very specific conditions. Therefore, the frequencies of adverse reactions observed in the clinical trials may not reflect frequencies observed in clinical practice and should not be compared to frequencies reported in clinical trials of another drug.
The following adverse events were observed in patients receiving zopiclone tablets. In the absence of an established cause-effect relationship those adverse reactions that were observed more frequently with zopiclone tablets than with a placebo are in italic.
Central Nervous System: Somnolence, dizziness, confusion, anterograde amnesia or memory impairment, feeling of drunkenness, euphoria, nightmares, agitation, anxiety or nervousness, hostility, depression, decreased libido, libido disorder, coordination abnormality, headache, hypotonia, tremor, muscle spasms, paresthesia, and speech disorder.
Hallucinations, aggression, irritability and fall (predominantly in elderly patients).
Cardiovascular: palpitations
Digestive: dysgeusia (bitter taste), dry mouth, coated tongue, bad breath, nausea, vomiting, diarrhea, constipation, anorexia or increased appetite
General Disorders and
Administration Site
Conditions: asthenia, chills, fatigue
Respiratory: dyspnea
Special senses: amblyopia
Dermatologic: rash, spots on skin, sweating, pruritus. Rashes and pruritus may be a sign of drug hypersensitivity; discontinue if this occurs.
Angioedema and/or anaphylactic reactions have been reported very rarely.
Metabolic and nutritional: weight loss
Musculoskeletal: limb heaviness
Geriatric patients
Geriatric patients tended to have a higher incidence of palpitations, vomiting, anorexia, sialorrhea, confusion, agitation, anxiety, tremor and sweating than younger patients. Anterograde amnesia is a dose-related phenomenon and elderly subjects may be at particular risk.
Withdrawal symptoms
Withdrawal syndrome has been reported upon discontinuation of zopiclone tablets (see 7 Warnings and Precautions, Withdrawal). Withdrawal symptoms vary and may include rebound insomnia, muscle pain, anxiety, tremor, sweating, agitation, confusion, headache, palpitations, tachycardia, delirium, nightmares, irritability. In severe cases the following symptoms may occur: derealisation, depersonalisation, hyperacusis, numbness and tingling of the extremities, hypersensitivity to light, noise and physical contact, hallucinations. In very rare cases, seizures may occur.
8.4 Abnormal Laboratory Findings: Hematologic, Clinical Chemistry and, Other Quantitative Data
Clinical Trial Findings
There have been sporadic reports of abnormal laboratory test values. Mild to moderate increases in serum transaminase and/or blood alkaline phosphatase have been reported very rarely.
8.5 Post-Market Adverse Reactions
Injury, Poisoning and Procedural Complications: There have been reports of falls and fractures in users of benzodiazepines or other sedative-hypnotic drugs, such as zopiclone tablets, due to adverse reactions such as sedation, dizziness and ataxia. The risk is increased in those taking concomitant sedatives (including alcoholic beverages), geriatric and debilitated patients.
Dependence/Withdrawal: Development of physical dependence and withdrawal following discontinuation of therapy has been observed with benzodiazepines or other sedative-hypnotic drugs, such as zopiclone tablets. Severe and life-threatening symptoms have been reported. (see 3 Serious Warnings and Precautions Box, Addiction, Abuse and Misuse; 7 Warnings and Precautions, Dependence, Tolerance and/or Abuse Liability).
Psychiatric disorders: restlessness, delirium, delusion, anger, abnormal behaviours (possibly associated with amnesia), complex sleep behaviours including somnambulism (see 7 Warnings and Precautions, Complex Sleep Behaviours), withdrawal syndrome and dependence have been reported rarely.
Respiratory disorders: respiratory depression
Nervous system disorder: ataxia, paresthesia (not associated with withdrawal), disturbance in attention
Eye disorder: diplopia
Gastrointestinal disorders: dyspepsia
Musculoskeletal and connective tissue disorders: muscular weakness.
9 Drug Interactions
9.1 Serious Drug Interactions
Concomitant use of ZOPICLONE and opioids may result in profound sedation, respiratory depression, coma and death.
(see 7 Warnings and Precautions, General, Risks from Concomitant Use with Opioids) |
|---|
9.2 Drug Interactions Overview
The risk of drug interaction arising from displacement of bound drug is low.
ZOPICLONE may produce additive CNS depressant effects when co-administered with alcohol, sedative antihistamines, anticonvulsants, narcotic analgesics, anesthetics, or psychotropic medications which themselves can produce CNS depression (see 9.3 Drug-Behaviour Interactions; 9.4 Drug-Drug Interactions).
The activity of ZOPICLONE may be increased or decreased when co-administered with CYP3A4 inhibitors or inducers respectively (see 9.4 Drug-Drug Interactions).
9.3 Drug-Behaviour Interactions
Alcohol
Concomitant intake with alcohol is not recommended (see 7 Warnings and Precautions, Complex Sleep behaviours). ZOPICLONE may produce additive CNS depressant effects when co-administered with alcohol.
9.4 Drug-Drug Interactions
CNS Depressants
ZOPICLONE may produce additive CNS depressant effects when co-administered with sedative antihistamines, anticonvulsants, narcotic analgesics, anesthetics, or psychotropic medications such as antipsychotics (neuroleptics), hypnotics, anxiolytics/sedatives, and antidepressant agents which themselves can produce CNS depression. In the case of narcotic analgesics, enhancement of euphoria may also occur, leading to an increase in psychological dependence.
Drugs Affecting Cytochrome P450 Enzymes
Since zopiclone is metabolized by the cytochrome P450 (CYP) 3A4 isoenzyme (see 10 Clinical Pharmacology, Pharmacokinetics, Metabolism), plasma levels of zopiclone may be increased when co-administered with CYP3A4 inhibitors, such as erythromycin, clarithromycin, ketoconazole, itraconazole, and ritonavir. A dose reduction for ZOPICLONE may be required when it is co-administered with CYP3A4 inhibitors. Conversely, plasma levels of zopiclone may be decreased when co-administered with CYP3A4 inducers, such as rifampicin or rifampin, carbamazepine, phenobarbital, phenytoin, and St. John’s wort. A dose increase for ZOPICLONE may be required when it is co-administered with CYP3A4 inducers (see 7 Warnings and Precautions).
The effect of erythromycin on the pharmacokinetics of zopiclone tablets has been studied in 10 healthy subjects. The AUC of zopiclone is increased by 80% in presence of erythromycin, a possible consequence of erythromycin inhibition of zopiclone metabolism by CYP3A4. As a consequence, the hypnotic effect of ZOPICLONE may be enhanced when administered with erythromycin or other CYP3A4 inhibitors.
Opioids
Due to additive CNS depressant effect, the concomitant use of benzodiazepines or other CNS depressants, including ZOPICLONE, and opioids increases the risk of profound sedation, respiratory depression, coma, and death. Reserve concomitant prescribing of these drugs for use in patients for whom alternative treatment options are inadequate. Limit dosages and durations of concomitant use of benzodiazepines and opioids to the minimum required. Follow patients closely for respiratory depression and sedation (see
3 Serious Warnings and Precautions Box, and 7 Warnings and Precautions, Concomitant Use with Opioids).
9.5 Drug-Food Interactions
Interactions with food have not been established.
9.6 Drug-Herb Interactions
Plasma levels of zopiclone may be decreased when co-administered with St. John’s wort.
9.7 Drug-Laboratory Test Interactions
Interactions with laboratory tests have not been established.
10 Clinical Pharmacology
10.1 Mechanism of Action
ZOPICLONE (zopiclone), a cyclopyrrolone derivative, is a short-acting hypnotic agent. Zopiclone is structurally unrelated to existing hypnotics. However, the pharmacological profile of zopiclone is similar to that of the benzodiazepines.
Zopiclone pharmacological properties are: hypnotic, sedative, anxiolytic, anti-convulsant, muscle-relaxant. These effects are related to a specific agonist action at central receptors belonging to the GABAA macromolecular complex, modulating the opening of the chloride ion channel.
Receptor binding studies
Zopiclone has a high and specific affinity for benzodiazepine binding sites in several rat brain regions. The drug can inhibit the binding of 3H-benzodiazepines, but can itself label the sites that are recognized both by benzodiazepine agonists and Ro 15-1788, a benzodiazepine antagonist. Zopiclone does not recognize the peripheral benzodiazepine receptor sites and lacks affinity for the serotonin, GABA, α1 and α2 adrenergic, and dopamine receptors.
The interaction of zopiclone with the benzodiazepine receptor/GABA receptor/chloride channel complex differs somewhat from that of the benzodiazepines; while it decreases cGMP concentration in rat cerebellum, its binding is not enhanced either by GABA or by the chloride anion.
10.2 Pharmacodynamics
In sleep laboratory studies of one to 21-day duration in man, zopiclone reduced sleep latency, increased the duration of sleep and decreased the number of nocturnal awakenings. Zopiclone delayed the onset of REM sleep but did not reduce consistently the total duration of REM periods. The duration of stage 1 sleep was shortened, and the time spent in stage 2 sleep increased. In most studies, stage 3 and 4 sleep tended to be increased, but no change and actual decreases have also been observed. The effect of zopiclone on stage 3 and 4 sleep differs from that of the benzodiazepines, which suppress slow wave sleep. The clinical significance of this finding is not known.
With hypnotic drugs, the duration of hypnotic effect and the profile of unwanted effects may be influenced by the alpha (distribution) (t½α) and beta (elimination) (t½β) half-lives of the administered drug and any active metabolites formed. When half-lives are long, the drug or metabolite may accumulate during periods of nightly administration and be associated with impairments of cognitive and motor performance during waking hours. If half-lives are short, the drug and metabolites will be cleared before the next dose is ingested, and carry-over effects related to sedation or CNS depression should be minimal or absent. If the drug has a very short elimination half-life, it is possible that a relative deficiency (i.e., in relation to the receptor site) may occur at some point in the interval between each night's use. This sequence of events may account for two clinical findings reported to occur after several weeks of nightly use of rapidly eliminated benzodiazepines or benzodiazepine-like hypnotics: 1) increased wakefulness during the last third of the night and 2) the appearance of increased day-time anxiety (see 7 Warnings and Precautions).
During nightly use and for an extended period, pharmacodynamic tolerance or adaptation to some effects of benzodiazepines or benzodiazepine-like hypnotics may develop. However in two sleep laboratory studies involving 17 patients, there was an absence of tolerance with zopiclone for treatment periods of more than 4 weeks.
CNS Activity
Zopiclone antagonizes chemically and electroshock-induced seizures in mice and rats. While it potently affects convulsive conditions that involve GABA, it is relatively ineffective when glycine, another inhibitory amino acid, is involved.
Zopiclone exerts muscle relaxant activity; it inhibits the traction grasping reflex in mice, reduces the ability of mice and rats to remain on a rotarod and inclined screen, respectively, relaxes the hind legs of normal cats and blocks polysynaptic reflexes in chloralosed cats.
Zopiclone also exerts antiaggressive activity; it inhibits footshock-induced fighting behaviour in mice and septal lesion-induced aggression in rats.
In a "conflict" situation, the drug increases punishment-suppressed lever-pressing behaviour, which is indicative of anxiolytic activity. Non-punished responding, indicative of non-specific sedation, is suppressed only at higher doses.
While zopiclone does not cause loss of righting reflex in normal mice, it potentiates narcosis induced by hexobarbital or ethanol.
In a drug discrimination paradigm, where rats are trained to discriminate drug from saline, the zopiclone discriminative stimulus generalized to several benzodiazepines as well as to pentobarbital. The finding that the benzodiazepines and a barbiturate were able to substitute for zopiclone indicates that zopiclone belongs to the same class of drugs.
Tolerance does not develop to the behavioural effects of zopiclone, since the anticonvulsant and taming ED50's are similar in naive and zopiclone-treated animals.
Dependence Liability
In barbital-dependent rhesus monkeys, zopiclone suppressed the abstinence symptoms which appeared upon withdrawal. Partial and complete suppression was observed at 4 and 16 mg/kg doses, respectively.
Zopiclone, when administered to monkeys at a dose of 16 mg/kg/day for 28 days, precipitated withdrawal signs of moderate severity. Peak symptoms appeared three and four days after withdrawal and included hyperirritability, restlessness, tremor, and some weight loss. The administration of a higher dose for two weeks brought about similar symptoms upon withdrawal without precipitating convulsions.
Zopiclone was self-administered both intravenously and intragastrically in monkeys. When the drug was changed to saline, the rate of self-administration declined rapidly.
Rebound insomnia: Some manifestations of rebound insomnia have been reported both in sleep laboratory and clinical studies following the withdrawal of zopiclone (see 7 Warnings and Precautions).
Zopiclone treatment was associated with dose-related residual effects (see 7 Warnings and Precautions).
Cardiovascular and Respiratory Effects
Zopiclone was evaluated in conscious and anesthetized cats, dogs, rabbits and monkeys with regard to its effect on respiration and several cardiovascular parameters. Most of the studies involved i.v. administration.
In general, respiration and blood pressure decreased in a dose-dependent fashion while heart rate and EKG showed little change. Zopiclone affected central respiratory control mechanisms to a greater extent than the cardiovascular regulatory mechanisms.
Drug-Interaction Studies
Zopiclone was evaluated in combination with several drugs and in general interacted either in an additive or synergistic fashion with diazepam, phenobarbital, trimethadione, chlorpromazine, hexobarbital, and ethanol. Zopiclone did not modify the effects of phenytoin, morphine, ketoprofen and gallamine.
The effects of zopiclone could be reversed by Ro 15-1788 (flumazenil) a specific benzodiazepine antagonist.
10.3 Pharmacokinetics
Absorption
Zopiclone is rapidly and well absorbed. Bioavailability is more than 75%, indicating the absence of a significant first-pass effect. After the administration of 3.75 and 7.5 mg doses, peak plasma concentrations of 30 and 60 ng/mL, respectively were reached in less than 2 hours. Absorption was similar in males and females.
Repeated daily administration of a 7.5 mg oral dose for 14 days did not change the pharmacokinetic characteristics of zopiclone and did not lead to accumulation.
Distribution
Zopiclone is rapidly distributed from the vascular compartment (distribution half-life [t½α]: 1.2 hours) while the elimination half-life is approximately 5 hours (range: 3.8 to 6.5 hours). Plasma protein binding is low (approximately 45% in the 25 to 100 ng/mL concentration range) and non saturable. The risk of drug interaction arising from displacement of bound drug is low. The distribution volume is 91.8 to 104.6 liters.
Metabolism
Zopiclone is extensively metabolized by three major pathways; only about 4 to 5% of the drug is excreted unchanged in the urine.
An in vitro study indicates that cytochrome P450 (CYP) 3A4 is the major isoenzyme involved in the metabolism of zopiclone to both metabolites, and that CYP2C8 is also involved with N-desmethyl zopiclone formation.
The principal metabolites are the N-oxide derivative (~12%), which has weak pharmacological activity in animals, and the N-desmethyl metabolite (~16%), which is pharmacologically inactive.
Their apparent half-lives evaluated from the urinary data are approximately 4.5 and 7.4 hours, respectively. Both metabolites are excreted renally.
Other metabolites resulting from oxidative decarboxylation are partly eliminated via the lung as carbon dioxide. In animals, zopiclone did not induce hepatic microsomal enzymes.
Elimination
Excretion studies, using C14-zopiclone have shown that more than 90% of the administered dose was excreted over a period of 5 days, 75% being eliminated in the urine and 16% in the feces.
The low renal clearance of unchanged zopiclone (mean 8.4 mL/min) compared with that of plasma (232 mL/min) indicates that zopiclone clearance is mainly metabolic.
Special Populations and Conditions
- Pediatrics: ZOPICLONE is not indicated for patients under 18 years of age.
- Geriatrics: the absolute bioavailability of zopiclone was increased (94% vs 77% in young subjects) and the elimination half-life prolonged (~7 hours). Accumulation has not been observed on repeated dosing.
- Pregnancy and breastfeeding: zopiclone was present in the milk, its concentration paralleled plasma levels but was about 50% lower (see 7 Warnings and Precautions).
Hepatic Insufficiency: elimination half-life was substantially prolonged (11.9 hours) and time to peak plasma levels delayed (3.5 hours). Consequently, lower doses are recommended (see 4 Dosage and Administration).
In cirrhotic patients, the plasma clearance of zopiclone is reduced by approximately 40% in relation with the decrease of the demethylation process. Therefore, dosage will have to be modified in these patients.
Renal Insufficiency: the pharmacokinetics of zopiclone were not affected by mild to moderate renal insufficiency. In renal insufficiency, no accumulation of zopiclone or of its metabolites has been detected after prolonged administration.
Zopiclone is removed by hemodialysis; however, hemodialysis is of no value in treating overdose due to the large volume of distribution of zopiclone tablets (see also 5 Overdose). Hemodialysis did not appear to increase the plasma clearance of the drug.
11 Storage, Stability, and Disposal
Store at room temperature 15°C to 30°C. Protect from light.
Keep out of reach and sight of children.
12 Special Handling Instructions
No special handling instructions information is required for this drug product.
Part 2: Scientific Information
13 Pharmaceutical Information
Drug Substance
Non-proprietary name of the drug substance: Zopiclone
Chemical name: 4-methyl-1-piperazinecarboxylic acid ester with 6-(5-chloro-2- pyridyl)-6,7-dihydro-7-hydroxy-5H-pyrrolo[3,4-b]pyrazin-5-one
Molecular formula and molecular mass: C17H17ClN6O3 and 388.82 g/mol
Structural formula:
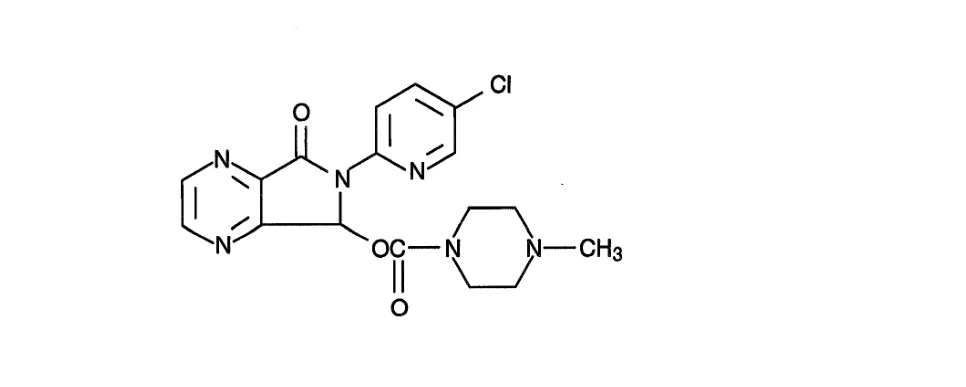
Physicochemical properties: Fine white odorless non hygroscopic powder. Melting point: 178°C. Zopiclone is freely soluble in chloroform and methylene chloride, soluble in dimethylformamide and 0.1 N hydrochloric acid, slightly soluble in acetone and practically insoluble in water, ethanol and ethyl ether.
14 Clinical Trials
14.1 Clinical Trials by Indication
Data on which indications were initially approved is not available.
14.2 Comparative Bioavailability Studies
A randomized, two-period, two-treatment, single dose (1 x 7.5 mg), crossover comparative bioavailability study of ZOPICLONE (Sivem Pharmaceuticals ULC) and IMOVANE® (Rhone-Poulenc Rorer Canada Inc.) was performed in healthy, human, subjects under fasting conditions.
A summary of the comparative bioavailability data from 21 subjects that were included in the statistical analysis are presented in the following tables:
Table - Summary Table of The Comparative Bioavailability Data
Zopiclone (1 x 7.5 mg) Geometric Mean Arithmetic Mean (CV %) | ||||
|---|---|---|---|---|
| Parameter | Test1 | Reference2 | % Ratio of Geometric Means | 90 % Confidence Interval |
AUCT (ng·h/mL) | 382.7 386.3 (15.7) | 385.7 391.4 (16.5) | 99.2 | 93.8 – 105.0 |
AUCI (ng·h/mL) | 408.1 412.3 (14.9) | 411.6 416.1 (15.4) | 99.5 | 94.5 – 104.8 |
Cmax (ng/mL) | 67.5 68.6 (18.5) | 66.0 66.7 (16.1) | 102.3 | 96.0 – 109.1 |
Tmax3 (h) | 1.00 (0.50 – 2.00) | 1.00 (0.50 – 4.00) | ||
T½4 (h) | 4.54 (17.57) | 4.59 (16.94) | ||
1 ZOPICLONE (zopiclone) tablets, 7.5 mg (Sivem Pharmaceuticals ULC)
2 IMOVANE® (zopiclone) tablets, 7.5 mg (Rhone-Poulenc Rorer Canada Inc.)
3 Expressed as the median (range) only
4 Expressed as arithmetic mean (CV %) only
15 Microbiology
No microbiological information is required for this drug product.
16 Non-Clinical Toxicology
General Toxicology
Acute
Studies were carried out in both sexes of several species. The results are summarized in the Table.
| SPECIES | ROUTE | LD50 (mg/kg) |
| Mice | i.v. i.p. p.o. | 450 580 1150 |
| Rats | p.o. | 2300 |
| Dogs | p.o. i.v. | ≥4500 ~400 |
| Cats | p.o. | >1500 |
| Rabbits | p.o. | ~2500 |
| Monkeys | p.o. | >4500 |
Symptoms of toxicity included sedation, CNS depression, ataxia, respiratory depression, and dyspnea. In dogs, the i.v. administration of zopiclone was followed by myoclonic seizures.
Long-Term
Rats (CD Strain):
One-month oral study
Ten rats/sex/dose received zopiclone by gavage six days per week at doses of 0, 6, 24 and 120 mg/kg. Dose-related sedation and paresis of hind legs were observed.
Thyroid weights were increased in male rats at all dose levels. In the high dose males, heart and spleen weights were reduced.
Three-month oral study
Fifteen rats/sex/dose received zopiclone by gavage seven days per week at doses of 0, 2, 12 and 120 mg/kg. At the mid and high doses, dose-related hypotonia, adynamia and ptosis were observed, all of which subsided with time. Weight gain was slightly but significantly less in mid and high dose male rats than in controls.
At the 120 mg/kg dose the following changes occurred. BSP values decreased in both sexes; the number of RBC decreased in females; liver weights increased in both males and females, accompanied by slight changes in the parenchymal liver cells, namely eosinophilia or basophilia in the portal area.
18-month oral study
Fifty rats/sex/dose received zopiclone in the diet at doses of 0, 2, 20 and 200 mg/kg. Of these animals 15 rats/sex/dose were sacrificed at six months. The lowest dose was well tolerated.
At the high dose the following changes were seen: weight gain was reduced by about 30% in both sexes; plasma protein levels were elevated at 3 and 6 months in the males and throughout the study in the females; albumin and globulin levels were elevated; thyroid weights were increased in male rats, accompanied by thyroid hyperplasia and, in some rats, by follicular adenomas; liver weights were increased in female rats both at 6 and 18 months; hepatocellular hypertrophy occurred in both sexes.
Dogs (Beagle):
One-month oral study
One dog/sex/dose received zopiclone six days per week at doses of 0, 6, 24 and 120 mg/kg. Dose-related sedation and hypotonia of the hind legs were observed. High dose dogs and the intermediate dose female dog exhibited moderate weight loss.
At the high dose, both dogs had Heinz bodies in circulating erythrocytes and the bone marrow showed erythroblastic hyperplasia. In addition, the male animal had marked anemia and active erythropoiesis in the spleen. BUN values were increased at all doses in a dose-related fashion; liver function tests were somewhat elevated.
Six-month oral study
Six dogs/sex/dose received zopiclone seven days per week at doses of 0, 5, 10 and 25 mg/kg. One dog/sex from each group was sacrificed after a 3-month recovery period. Zopiclone caused slight excitation, ataxia and drowsiness, and drowsiness and sleep at the 5, 10, and 25 mg/kg doses respectively. Late in the study, four dogs had epileptoid seizures and three of them died. A reduced weight gain was observed only in high dose male dogs.
Platelet counts rose substantially above normal in two high dose female dogs. Transaminase levels were elevated but not in a dose-dependent manner. Alkaline phosphatase levels were significantly elevated both in male and female dogs, receiving the 25 mg/kg dose.
While liver weights increased both in male and female dogs in a dose-dependent fashion, they returned toward control values following the 3-month recovery period. In high dose male animals, relative spleen, kidney and adrenal weights were significantly increased. Examination of bone marrow smears showed that the proportion of proerythroblasts and the ratio of normoblasts to basophilic erythroblasts were significantly greater in high dose females than in controls.
One-year oral study
Five dogs/sex/dose received zopiclone seven days per week at doses of 0, 1, 5 and 25 mg/kg. Zopiclone induced ataxia, sleepiness, lethargy, decreased activity, body tremors and excitability. The latter two effects occurred prior to dosing, while the others were seen shortly after dosing. After six months of treatment, zopiclone induced epileptoid seizures in five dogs (four high dose, one mid dose). Since the convulsions were observed early morning prior to dosing, they might have been a manifestation of withdrawal. Female dogs, treated with 5 mg/kg of zopiclone, were significantly heavier than controls. Treated animals both ate and drank more than did their respective controls.
Platelet counts were elevated in both sexes at the 5 and 25 mg/kg doses. Alkaline phosphatase was elevated from the first month on in mid and high dose animals. T4 values in high dose males and BSP values in high dose females were also elevated.
There was a dose-dependent increase in liver weights which became statistically significant at the 25 mg/kg dose. The elevated liver weights were associated with histopathological changes, namely vacuolation of hepatocyte cytoplasm with eosinophilic hyaline bodies.
Genotoxicity
Zopiclone and its metabolic products were tested for mutagenic potential in the following assays:
| ASSAY | INDICATOR SPECIES OR ORGANISM | DOSES USED |
| Ames' test | Salmonella typhimurium (TA98, TA100, TA1535, TA1537 & TA 1538) Escherichia coli (WP2 uvrA) | Up to 500 mcg/plate with or without rat liver microsome activating enzymes. |
| Ames' test | Salmonella typhimurium (5 strains as above) | Concentrated urine extracts from rats treated at 1, 10 and 100 mg/kg for 20 days. |
| Ames' test | Salmonella typhimurium (5 strains as above) | Up to 5000 mcg/plate with liver microsomal enzymes from B6C3F1 mice. |
| Ames' test | Salmonella typhimurium (5 strains as above) Escherichia coli (WP2 uvrA) |
DOSES USED |
| ASSAY | INDICATOR SPECIES OR ORGANISM | |
| ||
| In vitro and In vivo host mediated assay | Saccharomyces cerevisiae (D7) | In vitro: up to 1000 mcg/mL In vivo, in mice: 100 mg/kg p.o. |
| Gene forward mutation test | Chinese Hamster Ovary cells (CHO/HG PRT) | Up to 200 mcg/mL with or without metabolic activation. |
| In vitro mammalian cell test for clastogenicity. | Chinese Hamster Ovary cells (CHO/K1 line) | Up to 200 mcg/mL with or without metabolic activation. |
| DNA repair Assay (William's test) | Primary cultures of rat hepatocytes | Up to 10-4 M. |
| Dominant lethal test | Rats and mice | Up to 120 mg/kg/day p.o. |
| Micronucleus test | Mice | Up to 630 mg/kg/day p.o. |
| Sex-linked recessive lethal test | Drosophila melanogaster cells (CHO/HG PRT) | 2% solution p.o. activation. |
All tests were negative. Zopiclone was neither a mutagen nor a clastogen and did not give rise to mutagenic metabolites either in experimental animals or in man.
Carcinogenicity
Oncogenicity studies were carried out with zopiclone in rats and mice with doses of 1, 10, 100 mg/kg/day for two years. There was an increased incidence of mammary tumours with a shift toward more anaplastic forms in female and an increase of thyroid tumours in male rats on the high dose. In the mouse study, females on the high dose had an increased incidence of pulmonary adenocarcinomas; while males on the high dose had a high number of subcutaneous soft tissue tumours.
In a wide battery of tests, it was shown that zopiclone has no mutagenic or clastogenic (chromosome-damaging) properties; urine extracts from zopiclone treated mice, rats and humans were similarly not mutagenic.
The effect of zopiclone is that of a non-genotoxic oncogen; tumor redistribution phenomena are frequently observed in rodent carcinogenicity studies, particularly with drugs acting on the central nervous system and the hormonal balance. The rise of 17 beta-estradiol may be regarded as a cause for the emergence of mammary tumours and the shift from well differentiated to poorly differentiated mammary carcinomas. The altered feedback mechanism following accelerated clearance of T4 and the rise of TSH is responsible for thyroid overstimulation that leads to formation of thyroid neoplasms. The soft tissue tumours of male mice are brought about by fighting (a paradoxical reaction) and subsequent initiation by encrustation and foreign body reaction. The increased incidence of pulmonary adenocarcinomas in female mice may be regarded as fortuitous ("chance finding"), but there is not enough data available to exclude some other mechanisms.
No comparable endocrine changes were observed in man given the therapeutic dose of zopiclone (7.5 mg). The tumor producing dose of zopiclone represents 800 times and the no effect level 80 times the proposed human dose (0.125 mg/kg).
Reproductive and Developmental Toxicology
Fertility and general reproductive performance
The effect of zopiclone was evaluated in three studies. First, treated male rats were mated with treated female rats, the oral doses of zopiclone being 0, 2, 12 and 120 mg/kg. The males were treated for 10 weeks prior to mating, the females for 2 weeks prior to mating, during pregnancy and throughout a 3-week lactation period. In two further experiments, treated males (120 mg/kg) were mated with untreated females and untreated males were mated with treated females (120 mg/kg). Both of the latter experimental conditions included a control group.
Rate of pregnancy, number of implantations, rate of resorption and number of live fetuses were similar in control and low and medium dose-treated rats. However, mortality of pups was significantly higher in the mid dose group than in the control group.
At the 120 mg/kg dose, regardless whether treated males were mated with treated or untreated females, only ~10% of the females became pregnant and even in these animals resorption was complete. When high dose-treated females were mated with untreated males, the rate of pregnancy was only slightly lower than in controls (83% vs 100%) and all pregnant females delivered live fetuses. Survival of fetuses, up to day 21 of lactation, was significantly lower than in controls.
In conclusion, a 120 mg/kg dose of zopiclone induces sterility in male animals, while in females it affects pregnancy rate only slightly. Up to 12 mg/kg, the drug does not affect fertility and reproductive functions.
Teratology - rats
The study was performed in groups of 20 rats each, given zopiclone orally at doses of 0, 5, 25 and 125 mg/kg from day 5 to day 15 of gestation. In rats treated with the high dose of zopiclone, the following changes were seen when compared to the controls: food intake and final body weight (day 20) were slightly but significantly lower, the rate of resorption was somewhat higher (9% vs 6%) and the mean weight of live fetuses slightly but significantly lower (3.5 g vs 3.7 g). One pup had a sternal malformation, and five pups from the same mother had asymmetrical sternebrae. Both anomalies occur in the strain used. In conclusion, zopiclone is not teratogenic in rats in doses up to 125 mg/kg.
Teratology - rabbits
The study was performed in groups of 16 rabbits each given zopiclone orally at doses of 0, 5, 25 and 125 mg/kg from day 6 to day 16 of gestation. Food intake and weight gain were significantly affected and in a dose-related manner. At the 125 mg/kg dose, the rabbits actually lost some weight by the end of treatment. The mean weight of live fetuses in this group was significantly lower than in the controls (31.5 g vs 35.8 g). Three of the fetuses were malformed, 1/109 live fetuses in the mid dose and 2/129 live fetuses in the high dose, exhibiting malformations of the urinary tract, exencephaly and forelimbs with clubfeet and malformations of the large heart vessels, respectively. These malformations do occur in the strain used. In conclusion, zopiclone is not teratogenic in rabbits in doses up to 125 mg/kg.
Perinatal and postnatal study
This was a two generation study in which male and female offsprings (F1 generation) of treated mothers were bred and the F2 generation also observed.
Zopiclone was given orally at doses of 0, 10, 50 and 250 mg/kg from day 17 of gestation to day 28 of lactation. The following significant changes were observed: smaller litter size in the high dose group, lower body weights at birth and at weaning in the mid and high dose groups, dose-related increase of mortality at birth and between days 1 and 28. Mortality during lactation was significantly different from control even in the 10 mg/kg group. Cannibalization of pups increased in a dose-related manner; this effect might have been due to the fact that the pups were sedated, hypothermic and had problems with suckling.
Gross behaviour, physical development, auditory function, spontaneous motor activity and learning behaviour were normal in the surviving F1 pups. Males and females from the F1 generation mated successfully except for three rats which were infertile (one male rat from the 50 mg/kg group and one male and one female rat from the 250 mg/kg group). The male rat from the mid dose group had bilateral hypoplastic testes and epididymis. Mortality and weights of the F2 generation were within the normal range for the strain used. One F2 pup, from the mid dose group, had oligodactyly with syndactyly of the left forelimb.
17 Supporting Product Monographs
- 1. IMOVANE® (Tablets, 7.5 mg), control 300774, product monograph, Sanofi-Aventis Canada Inc. (2025-12-24)