


Product Monograph - Abbott-Rabeprazole
SUMMARY PRODUCT INFORMATION
| Route of Administration | Dosage Form / Strength | Clinically Relevant Nonmedicinal Ingredients |
| Oral | Tablet 10 mg , 20 mg | None Nonmedicinal Ingredients: Diethyl Phthalate, Ethyl Cellulose (7 cps), Ferric Oxide Red, Ferric Oxide Yellow, Hypromellose Phthalate, Mannitol, Magnesium Oxide, Magnesium Stearate, Povidone, Sodium Starch Glycolate, Talc, Titanium Dioxide and OPACODE monogramming ink S-1-17823 Black (Shellac glaze, iron oxide black and propylene glycol). |
INDICATIONS AND CLINICAL USE
Abbott-Rabeprazole is indicated for:
treatment of conditions where a reduction of gastric acid secretion is required, such as:
- 1.
Symptomatic relief and healing of erosive or ulcerative gastroesophageal reflux disease
(GERD).
- 2. Long-term maintenance of healing of erosive or ulcerative gastroesophageal reflux disease (GERD).
- 3. Treatment of symptoms (i.e. heartburn and regurgitation) in symptomatic gastroesophageal reflux disease (GERD), also called non-erosive reflux disease (NERD).
- 4. Symptomatic relief and healing of duodenal ulcers.
- 5. Symptomatic relief and healing of gastric ulcers.
- 6.
Long-term treatment of pathological hypersecretory conditions, including Zollinger-
Ellison syndrome.
- 7. Eradication of H. pylori associated with duodenal ulcer disease (active or history within the past 5 years). Eradication of H. pylori has been shown to reduce the risk of duodenal ulcer recurrence. Clinical trials using combinations of rabeprazole with appropriate antibiotics have indicated that such combinations are successful in eradicating H. pylori. Presented below in Table 1.1 are the data from a U.S. multicentre study (Study 604) comparing rabeprazole, amoxicillin, and clarithromycin (RAC) for 3, 7 or 10 days versus omeprazole, amoxicillin and clarithromycin (OAC) for 10 days. In a European multicentre study (Study 603), RAC was compared to OAC for 7 days.
- 1.
Table 1.1: H. pylori eradication† rates with rabeprazole or omeprazole plus amoxicillin and clarithromycin in patients with duodenal ulcer disease
| Proton Pump Inhibitor in Treatment | Treatment Time | % of Patients Cured [95% Confidence Interval of the difference RAC-OAC] (Number of patients) | ||
| Per-Protocol‡ | Intent-to-Treat†† | |||
Study 604 North America | Rabeprazole | 3 days | 30% [-61%, -43%] (n=167) | 27% [-55%, -37%] (n=187) |
| Rabeprazole | 7 days | 84%* [-5%, +11%] (n=166) | 77%* [-4%, +12%] (n=194) | |
| Rabeprazole | 10 days | 86%* [-3%, +12%] (n=171) | 78%* [-4%, +13%] (n=196) | |
| Omeprazole | 10 days | 82% (n=179) | 73% (n=206) | |
| Study 603 Europe | Rabeprazole | 7 days | 94% [-0.7%, +20%] (n=65) | 84% [+0.5%, +24.5%] (n=83) |
| Omeprazole | 7 days | 84% (n=63) | 72% (n=85) | |
† In Study 604, H. pylori eradication was assessed at 6 weeks but not more than 10 weeks by 13C-UBT. In Study 603, successful eradication of H. pylori was defined as a negative 13C-UBT at week 5 and week 13 post-treatment assessments.
‡ Patients were included in the analysis if they had H. pylori infection documented at baseline, defined as a positive 13C-UBT plus rapid urease test or culture and were not protocol violators. Patients who dropped out of the study due to an adverse event related to the study drug were included in the evaluable analysis as failures of therapy.
†† Patients were included in the analysis if they had documented H. pylori infection at baseline defined as a positive 13C-UBT plus rapid urease test or culture, and took at least one dose of study medication.
* Equivalent to OAC; two-sided 95% confidence interval on the difference between regimens is within [-15%, +15%].
Geriatrics: See WARNINGS AND PRECAUTIONS, Special Populations
Pediatrics (< 18 years of age): The safety and efficacy of Abbott-Rabeprazole have not been established in children under the age of 18 years.
CONTRAINDICATIONS
- Patients who are hypersensitive to rabeprazole, substituted benzimidazoles, or to any ingredient in the formulation or component of the container. For a complete listing, see the DOSAGE FORMS, COMPOSITION AND PACKAGING section of the Product Monograph;
Amoxicillin is contraindicated in patients with a known hypersensitivity to any penicillin.
(Please refer to the amoxicillin Product Monograph before prescribing);
- Clarithromycin is contraindicated in patients with known hypersensitivity to clarithromycin, erythromycin or other macrolide antibacterial agents. Clarithromycin is also contraindicated in patients receiving concurrent therapy with astemizole, terfenadine, cisapride or pimozide. (Please refer to the clarithromycin tablets Product Monograph before prescribing).
WARNINGS AND PRECAUTIONS
When gastric ulcer is suspected, the possibility of malignancy should be excluded before therapy with Abbott-Rabeprazole is instituted, as treatment with rabeprazole may alleviate symptoms and delay diagnosis.
General
Symptomatic response to therapy with Abbott-Rabeprazole does not preclude the presence of gastric malignancy.
Steady state interactions of rabeprazole and warfarin have not been adequately evaluated in patients. There have been reports of increased INR and prothrombin time in patients receiving proton pump inhibitors, including rabeprazole, and warfarin concomitantly. Increases in INR and prothrombin time may lead to abnormal bleeding and even death. Patients treated with a proton pump inhibitor and warfarin concomitantly may need to be monitored for increases in INR and prothrombin time.
Pseudomembranous colitis has been reported with nearly all antibacterial agents, including clarithromycin and amoxicillin, and may range in severity from mild to life threatening. Therefore, it is important to consider this diagnosis in patients who present with diarrhea subsequent to the administration of antibacterial agents.
Treatment with antibacterial agents alters the normal flora of the colon and may permit overgrowth of Clostridia. Studies indicate that a toxin produced by Clostridium difficile is a primary cause of “antibiotic-associated colitis”.
After the diagnosis of pseudomembranous colitis has been established, therapeutic measures should be initiated. Mild cases of pseudomembranous colitis usually respond to discontinuation of the drug alone. In moderate to severe cases, consideration should be given to management with fluids and electrolytes, protein supplementation, and treatment with an antibacterial drug clinically effective against Clostridium difficile colitis.
Decreased gastric acidity due to any means, including proton pump inhibitors, increases gastric counts of bacteria normally present in the gastrointestinal tract. Treatment with proton pump inhibitors may lead to slightly increased risk of gastrointestinal infections such as Salmonella and Campylobacter and possibly Clostridium difficile.
As demonstrated with other proton pump inhibitors (PPI’s), prolonged use may impair the absorption of protein-bound Vitamin B12 and may contribute to the development of Vitamin B12 deficiency.
Literature suggests that concomitant use of PPIs with methotrexate (primarily at high dose) may elevate and prolong serum levels of methotrexate and/or its metabolite, possibly leading to methotrexate toxicities. A temporary withdrawal of the PPI may be considered in some patients receiving treatments with high dose methotrexate.
Bone Fracture: Several published observational studies suggest that proton pump inhibitor (PPI) therapy may be associated with an increased risk for osteoporosis- related fractures of the hip, wrist or spine. The risk of fracture was increased in patients who received high dose, defined as multiple daily doses and long term PPI therapy (a year or longer). Patients should use the lowest dose and shortest duration of PPI therapy appropriate to the condition being treated. Patients at risk for osteoporosis-related fractures should be managed according to established treatment guidelines (see DOSAGE AND ADMINISTRATION, Recommended Dose and Dosage Adjustment and ADVERSE REACTIONS).
Endocrine and Metabolism
Hypomagnesemia: Hypomagnesemia, symptomatic and asymptomatic, has been reported rarely in patients treated with PPIs for at least three months, in most cases after a year of therapy. Serious adverse events include tetany, arrhythmias, and seizures. In most patients, treatment of hypomagnesemia required magnesium replacement and discontinuation of the PPI.
For patients expected to be on prolonged treatment or who take PPIs with medications such as digoxin or drugs that may cause hypomagnesemia (e.g., diuretics), health care professionals may consider monitoring magnesium levels prior to initiation of PPI treatment and periodically (see ADVERSE REACTIONS, Post-Market Adverse Drug Reactions).
The chronic use of PPIs may lead to hypomagnesemia. Moreover, hypokalemia and hypocalcemia have been reported in the literature as accompanying electrolyte disorders.
Hepatic/Biliary/Pancreatic
For patients with severe liver disease, dosage adjustment should be considered.
Renal
No dosage adjustment is necessary in patients with renal insufficiency.
Special Populations
Pregnant Women: The safety of Abbott-Rabeprazole treatment in pregnancy has not been established. Abbott-Rabeprazole tablets should not be administered to pregnant women unless the expected benefits outweigh the potential risks to the fetus.
Nursing Women: It is not known whether Rabeprazole Sodium is excreted in human milk. Abbott-Rabeprazole tablets should not be given to nursing mothers unless the expected benefits outweigh the potential risks to the infant.
Pediatrics (< 18 years of age): The safety and efficacy of rabeprazole have not been established in children under the age of 18 years.
Geriatrics: (>71 years of age): Benefits of use of PPIs should be weighed against the increased risk of fractures as patients in this category may already be at high risk of osteoporosis-related fractures. If the use of PPIs is required, they should be managed carefully according to established treatment guidelines (see ADVERSE REACTIONS, Post-Market Adverse Drug Reactions and DOSAGE AND ADMINISTRATION, Recommended Dose and Dosage Adjustment).
Ulcer healing rates in elderly patients are similar to those in younger patients. Adverse events and laboratory test abnormalities in elderly patients occurred at rates similar to those in younger patients. No dose adjustment is required in elderly patients.
ADVERSE REACTIONS
Adverse Drug Reaction Overview
Worldwide, over 3,094 patients have been treated with rabeprazole sodium in Phase II-III clinical trials involving various dosages and durations of treatment. In general, rabeprazole sodium treatment has been well tolerated in both short-term and long-term trials.
Clinical Trial Adverse Drug Reactions
Because clinical trials are conducted under very specific conditions the adverse reaction rates observed in the clinical trials may not reflect the rates observed in practice and should not be compared to the rates in the clinical trials of another drug. Adverse drug reaction information from clinical trials is useful for identifying drug-related adverse events and for approximating rates.
Incidence in North American and European Clinical Trials
The following adverse events were reported by the treating physicians to have a possible or probable relationship to drug in at least 1% of patients treated with rabeprazole sodium compared to patients who received placebo:
Table 1.2: Incidence of Possibly- or Probably-Related Adverse Events in Short-Term and Long-Term Controlled North American and European Studies
Rabeprazole Sodium n=1746 (%) | Placebo n=388 (%) | |
Body as a Whole Headache Digestive System Diarrhea | 2.8 2.6 | 2.8 2.3 |
Less Common Clinical Trial Adverse Drug Reactions (<1%)
In short- and long-term studies, the following adverse events were reported in <1% of the patients treated with rabeprazole sodium without regard to causality:
Body as a Whole:
enlarged abdomen, abscess, ascites, carcinoma, substernal chest pain, asthenia, allergic reaction, fever, chills, cellulitis, cyst, hangover effect, hernia, injection site hemorrhage, injection site pain, injection site reaction, malaise, moniliasis, mucous membrane disorder, neck pain, neck rigidity, neoplasm, overdose, pelvic pain, photosensitivity, suicide attempt.
Cardiovascular
System:
angina pectoris, arrhythmia, bradycardia, bundle branch block, cardiovascular disorder, coronary artery disorder, abnormal electrocardiogram, embolus, hypertension, increased capillary fragility, migraine, myocardial infarction, palpitation, QTc prolongation, sinus bradycardia, supraventricular tachycardia, syncope, tachycardia, thrombophlebitis, thrombosis, varicose vein, vascular disorder, ventricular extrasystoles, ventricular tachycardia.
Digestive System:
abdominal pain, abnormal stools, anorexia, bloody diarrhea, cholangitis, cholecystitis, cholelithiasis, cirrhosis of liver, colitis, constipation, diarrhea, duodenal ulcer, duodenitis, dry mouth, dyspepsia, dysphagia, esophageal stenosis, esophagitis, eructation, flatulence, gastritis, gastrointestinal hemorrhage, gastroenteritis, gastrointestinal carcinoma, gingivitis, glossitis, hepatic encephalopathy, hepatitis, hepatoma, increased appetite, melena, mouth ulceration, nausea and vomiting, pancreas disorder, pancreatitis, periodontal abscess, proctitis, rectal disorder, rectal hemorrhage, salivary gland enlargement, stomach ulcer, stomatitis, tooth caries, tooth disorder, ulcer ileum, ulcerative colitis, ulcerative stomatitis.
Endocrine System: diabetes mellitus, hyperthyroidism, hypothyroidism.
Hemic and
Lymphatic System:
anemia, ecchymosis, hypochromic anemia, lymphadenopathy.
Metabolic and
Nutritional
Disorders:
dehydration, edema, face edema, gout, iron deficiency anemia, liver fatty deposit, peripheral edema, thirst, weight gain, weight loss.
Musculoskeletal
System:
arthritis, arthrosis, bone pain, bursitis, joint disorder, leg cramps, myalgia, rheumatoid arthritis, tendon disorder.
Nervous System:
abnormal dreams, acute brain syndrome, addiction, agitation, amnesia, anxiety, cerebral hemorrhage, confusion, convulsion, dementia, depression, dizziness, extrapyramidal syndrome, hyperkinesia, hypertonia, insomnia, libido decreased, nervousness, neuralgia, neuropathy, paresthesia, sleep disorder, somnolence, tremor, twitching, vasodilatation, vertigo.
Respiratory System:
apnea, asthma, carcinoma of lung, dyspnea, epistaxis, hiccup, hyperventilation, hypoventilation, hypoxia, laryngitis, lung disorder, pneumonia, pulmonary embolus, respiratory disorder, voice alteration.
Skin and
Appendages:
acne, alopecia, benign skin neoplasm, contact dermatitis, dry skin, fungal dermatitis, herpes simplex, herpes zoster, nail disorder, pruritus, psoriasis, rash, seborrhea, skin carcinoma, skin discoloration, skin hypertrophy, skin melanoma, skin nodule, sweating, urticaria.
Special Senses: abnormal vision, amblyopia, blepharitis, blurry vision, cataract, conjunctivitis, corneal opacity, deafness, diplopia, dry eyes, ear disorder, ear pain, eye disorder, eye hemorrhage, eye pain, glaucoma, lacrimation disorder, otitis externa, otitis media, retinal degeneration, retinal disorder, strabismus, taste perversion, tinnitus, vestibular disorder, vitreous disorder.
Urogenital System:
breast enlargement, breast neoplasm, breast pain, cystitis, dysmenorrhea, dysuria, hematuria, impotence, kidney calculus, leukorrhea, mastitis, menorrhagia, menstrual disorder, metrorrhagia, orchitis, polycystic kidney, polyuria, prostatic disorder, urinary frequency, urinary incontinence, urinary tract disorder, uterine hemorrhage, vaginal hemorrhage, vaginitis.
Monitoring and Laboratory Tests
An extensive evaluation of laboratory analyses has not revealed any significant and/or clinically relevant changes during rabeprazole treatment. The following changes in laboratory parameters were reported as adverse events: abnormal platelets, albuminuria, increased creatine phosphokinase, abnormal erythrocytes, hypercholesteremia, hyperglycemia, hyperlipemia, hypokalemia, hyponatremia, leukocytosis, leukorrhea, abnormal liver function tests, prostatic specific antigen increase, urine abnormality, abnormal WBC.
In controlled clinical studies, 3/1456 (0.2%) patients treated with rabeprazole and 2/237 (0.8%) patients treated with placebo developed treatment-emergent abnormalities (which were either new on study or present at study entry with an increase of 1.25 x baseline value) in SGOT
(AST), SGPT (ALT), or both. None of the three rabeprazole patients experienced chills, fever, right upper quadrant pain, nausea or jaundice.
Combination Treatment with Amoxicillin and Clarithromycin
In clinical trials using combination therapy with rabeprazole plus amoxicillin and clarithromycin (RAC), no adverse events unique to this drug combination were observed. In the U.S. multicentre Study 604, the most frequently reported drug-related adverse events for patients who received the triple therapy for 7 or 10 days were diarrhea (8% and 7%) and taste perversion (6% and 10%), respectively. In the European multicentre Study 603, the most frequently occurring adverse events were diarrhea (13%) and taste perversion (14%) in patients receiving RAC therapy for 7 days.
No clinically significant laboratory abnormalities particular to the drug combinations were observed. When rabeprazole sodium is used in combination with amoxicillin and clarithromycin, the Product Monographs for those agents must be consulted and followed.
Post-Market Adverse Drug Reactions
Additional adverse events reported from worldwide marketing experience with rabeprazole sodium are: sudden death, coma and hyperammonemia, jaundice, rhabdomyolysis, disorientation and delirium, anaphylaxis, angioedema, bullous and other drug eruptions of the skin, interstitial pneumonia, TSH elevations, hypomagnesemia, osteoporosis, osteoporosis-related fractures, myalgia and arthralgia. In most instances, the relationship to rabeprazole sodium was unclear. There have also been rare reports of increased hepatic enzymes and rare reports of hepatitis. Rare reports of hepatic encephalopathy have been received in patients with underlying cirrhosis. In addition, agranulocytosis, hemolytic anemia, leukopenia, pancytopenia, thrombocytopenia, neutropenia and acute systemic allergic reactions (facial swelling, hypotension, dyspnea) have been reported. There have been very rare reports of interstitial nephritis, gynecomastia, erythema multiforme, toxic epidermal necrolysis and Stevens-Johnson syndrome.
Withdrawal of prolonged PPI therapy may result in a rebound acid hypersecretion (i.e., aggravation of acid-related symptoms) that can occur within days to weeks following PPI withdrawal and persist for 3-11 months.
DRUG INTERACTIONS
Rabeprazole is metabolized by the cytochrome P450 (CYP450) drug metabolizing system. Studies in healthy subjects have shown that rabeprazole does not have clinically significant interactions with other drugs metabolized by the CYP450 system, such as warfarin, phenytoin, theophylline or diazepam. Steady state interactions of rabeprazole and other drugs metabolized by this enzyme system have not been studied in patients. Studies with rabeprazole in humans reveal no inhibition or activation of the CYP450 system of the liver. There have been reports of increased INR and prothrombin time in patients receiving proton pump inhibitors, including rabeprazole, and warfarin concomitantly. Increases in INR and prothrombin time may lead to abnormal bleeding and even death. In vitro incubations employing human liver microsomes
indicated that the degree of inhibition of cyclosporin metabolism by rabeprazole and omeprazole is similar at equivalent concentrations.
Rabeprazole produces sustained inhibition of gastric acid secretion. An interaction with compounds whose absorption depends on gastric pH may occur due to the magnitude of acid suppression seen with rabeprazole: consequently, the co-administration of ketoconazole and rabeprazole decreases the absorption of ketoconazole, thereby decreasing plasma levels, whereas the concomitant use of digoxin results in an increase in digoxin plasma levels. Therefore, patients may need to be monitored when such drugs are taken concomitantly with rabeprazole.
Co-administration of atazanavir 300 mg/ritonavir 100 mg with omeprazole (40 mg once daily) or atazanavir 400 mg with lansoprazole (60 mg once daily) to healthy volunteers resulted in a substantial reduction in atazanavir exposure. The absorption of atazanavir is pH dependent. Although not studied, similar results are expected with other proton pump inhibitors. Therefore PPIs, including rabeprazole, should not be co-administered with atazanavir.
Case reports, published population pharmacokinetic studies, and retrospective analyses suggest that concomitant administration of PPIs and methotrexate (primarily at high dose) may elevate and prolong serum levels of methotrexate and/or its metabolite hydroxymethotrexate. However, no formal drug interaction studies of methotrexate with PPIs have been conducted.
Combination Therapy with Clarithromycin
Combination therapy consisting of rabeprazole, amoxicillin and clarithromycin resulted in increases in plasma levels of rabeprazole and 14-hydroxyclarithromycin. (see ACTION AND CLINICAL PHARMACOLOGY, Special Populations and Conditions, Combination Therapy with Antimicrobials).
Drug-Food Interactions
Taking rabeprazole with food or antacids produced no clinically relevant changes in plasma rabeprazole concentrations.
DOSAGE AND ADMINISTRATION
Recommended Dose and Dosage Adjustment
Patients should use the lowest dose and shortest duration of PPI therapy appropriate to the condition being treated.
Symptomatic Relief and Healing of Erosive or Ulcerative Gastroesophageal Reflux Disease (GERD)
The recommended adult oral dose is 20 mg once daily. In most patients, healing occurs in four weeks. For patients not healed after this initial course, an additional four weeks of treatment is recommended. Symptom relief is usually rapid. If symptom relief is not achieved after four weeks, further investigation is recommended (see INDICATIONS AND CLINICAL USE).
Long-term Maintenance of Healing of Erosive or Ulcerative Gastroesophageal Reflux Disease (GERD Maintenance)
10 mg once daily has been demonstrated to be effective versus placebo in the maintenance of healing of GERD. The maximum recommended adult oral dose is 20 mg once daily (see INDICATIONS AND CLINICAL USE).
Treatment of Symptoms (i.e. Heartburn and Regurgitation) of Symptomatic Gastroesophageal Reflux Disease (GERD) or Non-Erosive Reflux Disease (NERD)
The recommended adult oral dose is 10 mg once daily to a maximum of 20 mg once daily in patients with NERD. If symptom control is not achieved after four weeks, further investigation is recommended (see INDICATIONS AND CLINICAL USE).
Symptomatic Relief and Healing of Duodenal Ulcers
The recommended adult oral dose is 20 mg once daily for up to four weeks (see INDICATIONS AND CLINICAL USE). Most patients with duodenal ulcer heal within four weeks but a few patients may require additional therapy to achieve healing. Symptom relief is usually rapid with improvement achieved after two weeks for most patients.
Symptomatic Relief and Healing of Gastric Ulcers
The recommended adult oral dose is 20 mg once daily for up to six weeks (see INDICATIONS AND CLINICAL USE). Most patients with gastric ulcer heal within six weeks, but a few patients may require additional therapy to achieve healing. Symptom relief is usually rapid with improvement achieved after three weeks for most patients.
Eradication of H. pylori Associated with Duodenal Ulcer Disease - Triple Therapy: Rabeprazole 20 mg Twice Daily for 7 Days
Amoxicillin 1000 mg Twice Daily for 7 Days
Clarithromycin 500 mg Twice Daily for 7 Days
All three medications should be taken twice daily with the morning and evening meals.
In patients who fail therapy, susceptibility testing should be done. If resistance to clarithromycin is demonstrated or susceptibility testing is not possible, alternative antimicrobial therapy should be instituted.
Long-term Treatment of Pathological Hypersecretory Conditions Including Zollinger-Ellison Syndrome
The rabeprazole dosage in patients with pathologic hypersecretory conditions varies with the individual patient. The recommended adult oral starting dose is 60 mg once a day. Doses should be adjusted to individual patient needs and should continue for as long as clinically indicated. Some patients may require divided doses. Doses up to 100 mg QD and 60 mg BID have been administered. Some patients with Zollinger-Ellison syndrome have been treated continuously with rabeprazole tablets for up to one year.
No dosage adjustment is necessary in patients with renal insufficiency or in elderly patients. For patients with severe liver disease, dosage adjustment should be considered.
Administration
Abbott-Rabeprazole tablets can be taken with meals or on an empty stomach. Abbott-Rabeprazole tablets are enteric-coated and therefore should be swallowed whole with a beverage (not chewed or crushed).
OVERDOSAGE
There has been no experience with large overdoses of rabeprazole although seven reports of accidental overdosage with rabeprazole have been received. The maximum established exposure has not exceeded 60 mg twice daily or 160 mg once daily. Effects are generally minimal, representative of the known adverse event profile, and reversible without any further medical intervention. No specific antidote for rabeprazole is known; in the event of overdosage, treatment should be symptomatic and supportive. Rabeprazole is extensively protein-bound and is not readily dialyzable.
For management of a suspected drug overdose, contact your regional Poison Control Centre.
ACTION AND CLINICAL PHARMACOLOGY
Rabeprazole sodium is an antisecretory compound (substituted benzimidazole proton pump inhibitor) that suppresses gastric acid secretion by inhibiting the gastric H+, K+-ATPase at the secretory surface of the gastric parietal cell. Because this enzyme is regarded as the acid (proton) pump within the parietal cell, rabeprazole has been characterized as a gastric proton pump inhibitor. Rabeprazole Sodium blocks the final step of gastric acid secretion and produces dose-related sustained inhibition of both basal and stimulated gastric acid secretion.
Pharmacodynamics
Antisecretory Activity
The antisecretory effect begins within one hour after oral administration of rabeprazole sodium tablets (20 mg), and reaches its maximum within two to four hours. The median inhibitory effect of rabeprazole on 24-hour gastric acidity is 88% of maximal after the first dose and the inhibition of acid secretion increases with repeated once-daily dosing to steady-state within seven days. Rabeprazole 20 mg, versus placebo, inhibits basal and pentagastrin-induced acid secretion by 86% and 95%, respectively. At this dosage, it also increases the percentage of time (from 10% to 65%) within a 24-hour period with the gastric pH>3 (see Table 1.3). This relatively prolonged pharmacodynamic action compared to the short pharmacokinetic half-life (approximately one hour) reflects the sustained inactivation of the H+, K+-ATPase.
Table 1.3: Gastric Acid Parameters - Rabeprazole versus Placebo After 7 Days of Once-Daily Dosing
| Parameter | Rabeprazole (20 mg QD) | Placebo |
| Basal Acid Output (mmol/hr) Stimulated Acid Output (mmol/hr) | 0.4* 0.6* | 2.8 13.3 |
| % Time Gastric pH>3 | 65* | 10 |
*(p<0.01 versus placebo)
The ability of rabeprazole to cause a dose-related decrease in mean intragastric acidity is illustrated in Table 1.4.
Table 1.4: Mean AUC Acidity for Three Rabeprazole Doses versus Placebo
| Rabeprazole (mg QD) | ||||
| Parameter | 10 | 20 | 40 | Placebo |
| Mean AUC 0-24 acidity (mmol·hr/L) | 156* | 131* | 86* | 678 |
*(p<0.001 versus placebo)
The decrease in gastric acidity and the increase in gastric pH observed with 20 mg rabeprazole were compared to the same parameters with 20 mg omeprazole and placebo, as illustrated in Table 1.5.
Table 1.5: Gastric Acid Parameters - Rabeprazole versus Omeprazole and Placebo on Day 1 and Day 8 of Multiple Once-Daily Dosing
| Parameter | Rabeprazole 20 mg QD | Omeprazole 20 mg QD | Placebo |
| Day 1 Day 8 | Day 1 Day 8 | Day 1 Day 8 | |
| Mean AUC0-24 Acidity Median trough pH (23-hr)1 % Time Gastric pH>3 (1) % Time Gastric pH>4 (1) | 340.8*# 3.77 54.6*# 44.1*# 176.9*† 3.51 68.7*† 60.3*† | 577.1* 1.43 36.7* 24.7* 271.2* 3.21 59.4* 51.4* | 925.5 1.27 19.1 7.6 862.4 1.38 21.7 11.0 |
1No inferential statistics conducted for this parameter.
* (p<0.001) versus placebo
# (p<0.001) versus omeprazole 20 mg QD
† (p<0.05) versus omeprazole 20 mg QD
(1) Gastric pH was measured every hour over a 24-hour period.
Effects on Esophageal Acid Exposure
In patients with gastroesophageal reflux disease (GERD) and moderate to severe esophageal acid exposure, rabeprazole doses of 20 or 40 mg/day normalized 24-hour esophageal acid exposure. After seven days’ treatment, the percentage of time that the esophageal pH <4 was 5.1% at the 20 mg dose and 2.0% at the 40 mg dose, from baselines of 24.7% and 23.7%, respectively. Normalization of 24-hour intraesophageal acid exposure was correlated to gastric pH >4 for at least 35% of the 24-hour period; this level was achieved in 90% of subjects receiving a 20 mg rabeprazole dose and in 100% of subjects receiving a 40 mg rabeprazole dose. With rabeprazole doses of 20 or 40 mg/day, effects on gastric and esophageal pH were significant and substantial after one day of treatment and more pronounced after seven days of treatment.
Effects on Serum Gastrin
In patients given daily doses of rabeprazole tablets for up to eight weeks to treat ulcerative or erosive esophagitis and in patients treated for up to 52 weeks to prevent recurrence of disease, there was a dose-related increase in the median fasting gastrin level. The group median values stayed within the normal range. These data are indicative of dose-dependent inhibition on gastric acid secretion by rabeprazole tablets.
Effects on Enterochromaffin-like (ECL) Cells
Increased serum gastrin secondary to antisecretory agents stimulates proliferation of gastric ECL cells which, over time, may result in ECL cell hyperplasia in laboratory rats and mice and gastric carcinoids in laboratory rats. During life-time exposure of rats with doses of rabeprazole up to 120 mg/kg/day [60 times the exposure on a body surface (mg/m2) basis in patients given the recommended 20 mg/day (12.3 mg/m2) dose], ECL cell hyperplasia was observed in both male and female rats, while gastric carcinoids were observed in female Sprague Dawley rats only. ECL cell hyperplasia was observed with rabeprazole in both male and female rats and mice.
Human gastric biopsy specimens from the antrum and the fundus from 330 patients receiving rabeprazole treatment for up to 8 weeks detected no consistent pattern of changes in ECL cell histology. Histological findings from 61 patients receiving rabeprazole also showed no consistent pattern of changes in degree of gastritis. No chronic atrophic gastritis was found in these patients either at baseline or endpoint assessment. There was no consistent change in the incidence of intestinal metaplasia or distribution of H. pylori infection.
In over 400 patients undergoing rabeprazole treatment (10 or 20 mg/day) for up to one year, the incidence of ECL cell hyperplasia was low and comparable to that observed with omeprazole (20 mg/day); no patient demonstrated the adenomatoid changes or carcinoid tumour as observed in rats.
Endocrine Effects
Studies in humans for up to one year have revealed no clinically significant effects on the endocrine system. In healthy male volunteers treated with rabeprazole tablets for 13 days, no clinically relevant changes have been detected in the following endocrine parameters examined: 17 β-estradiol, thyroidstimulating hormone, tri-iodothyronine, thyroxine, thyroxine-binding protein, parathyroid hormone, insulin, glucagon, renin, aldosterone, follicle-stimulating hormone, luteotrophic hormone, prolactin, somatotrophic hormone, dehydroepiandrosterone, cortisol-binding globulin, urinary 6β-hydroxycortisol, and testosterone.
Other Effects
In humans treated with rabeprazole tablets for up to one year, no systemic effects have been observed on the central nervous system, lymphoid, hematopoietic, renal, hepatic, cardiovascular, ocular, or respiratory systems.
Microbiology
Rabeprazole sodium, amoxicillin and clarithromycin triple therapy has been shown to be active against most strains of Helicobacter pylori in vitro and in clinical infections as described in the INDICATIONS AND CLINICAL USE section and in Product Monograph Part II: CLINICAL TRIALS.
Pharmacokinetics
Abbott-Rabeprazole tablets are enteric-coated. Absorption is rapid following ingestion. After oral administration of 20 mg rabeprazole sodium, peak plasma concentrations (Cmax) are reached at an average of 1.6 - 5.0 hours; bioavailability compared to intravenous administration is 52%. Rabeprazole does not accumulate and its pharmacokinetics is not altered by multiple dosing. The plasma half-life is approximately one hour.
Absorption: Following oral administration, rabeprazole is rapidly absorbed and can be detected in plasma as early as 0.5 hours. The rabeprazole Cmax and AUC are linear with doses from 10 mg to 40 mg. Taking rabeprazole tablets with food does not alter Cmax or AUC relative to the fasting state; the Tmax is increased by 1.7 hours. Antacids do not significantly affect the absorption of rabeprazole sodium. Administration of rabeprazole sodium with a high fat meal may delay its absorption by approximately 4 hours or longer; however, the Cmax and the extent of absorption (AUC) are not altered.
Distribution: Rabeprazole is 96.3% bound to human plasma proteins.
Metabolism: In humans the thioether and carboxylic acid are the main plasma metabolites. These metabolites were not observed to have significant antisecretory activity. The sulphone, desmethylthioether and mercapturic acid conjugate minor metabolites were observed at lower levels. Only the desmethyl metabolite has a small amount of antisecretory activity, but it is not present in plasma.
In vitro studies have demonstrated that rabeprazole is metabolized primarily by non-enzymatic reduction to form the thioether metabolite. Rabeprazole is also metabolized in the liver by cytochromes P450 3A (CYP3A), to a sulphone metabolite, and cytochrome P450 2C19 (CYP2C19), to desmethyl rabeprazole. CYP2C19 exhibits a known genetic polymorphism due to its deficiency in some sub-populations (e.g. 3 to 5% of Caucasians and 17 to 20% of Asians). Rabeprazole metabolism is slow in these sub-populations; therefore, they are referred to as poor metabolizers of the drug.
Excretion: Following a single 20 mg 14C-labelled oral dose of rabeprazole sodium, no unchanged drug was excreted in the urine. Approximately 90% of the dose was eliminated in urine mainly as two metabolites: a mercapturic acid conjugate and a carboxylic acid; there are also two unknowns. The remainder of the dose was recovered in feces.
Special Populations and Conditions
Pediatrics: The pharmacokinetic profile of rabeprazole in adolescents and children under the age of 18 years has not been studied.
Geriatrics: In 20 healthy elderly subjects given a 20 mg rabeprazole dose once daily for seven days, AUC doubled and the Cmax increased by 60% compared to measurements in a parallel younger control group. There was no evidence of drug accumulation (see WARNINGS AND PRECAUTIONS).
Race: See Pharmacokinetics, Metabolism section.
Hepatic Insufficiency: In two studies, in which 23 patients with varying degrees of chronic compensated hepatic cirrhosis were given a 20 mg rabeprazole dose, the AUC of rabeprazole approximately doubled and the Cmax increased by 50% compared to measurements in healthy age- and sex-matched subjects.
Renal Insufficiency: In 10 patients with stable end-stage renal failure requiring maintenance hemodialysis (creatinine clearance ≤ 5 mL/min/1.73 m2), the pharmacokinetics of rabeprazole (rabeprazole 20 mg oral dose) were comparable to those in 10 healthy volunteers.
Combination Therapy with Antimicrobials: Sixteen healthy volunteers were given 20 mg rabeprazole sodium, 1000 mg amoxicillin, 500 mg clarithromycin, or the combination of all 3 rabeprazole, amoxicillin, and clarithromycin (RAC) in a four-way crossover study. Each of the four treatments was administered for 7 days with single doses administered on days 1 and 7 and twice daily on days 2-6. The AUC and Cmax for clarithromycin and amoxicillin were similar during combined treatment compared to monotherapy. The rabeprazole AUC and Cmax increased by 11% and 34%, respectively, and the 14-hydroxyclarithromycin (active metabolite of clarithromycin) AUC and Cmax increased by 42% and 46%, respectively, during the combined treatment compared to values obtained during monotherapy. This increase in exposure to rabeprazole and 14-hydroxyclarithromycin is not considered to be clinically significant.
In an open-label, randomized, four-period crossover study in 20 healthy Japanese volunteers, 16 extensive metabolizers (EM) and four poor metabolizers (PM) of CYP2C19 genotype were given 20 mg rabeprazole, 400 mg clarithromycin, 750 mg amoxicillin, or the combination of rabeprazole, amoxicillin and clarithromycin. Each of the treatments consisted of a single oral administration under fasting conditions on days 1 and 7, and twice daily administration on days 2 to 6. As illustrated in Table 1.6, in the EM and PM subjects, an interaction was observed for clarithromycin, 14-hydroxyclarithromycin, and rabeprazole which resulted in a higher Cmax and AUC0-12 during the combination treatment compared to monotherapy. For the amoxicillin treatment, no interaction was observed in the PM subjects, and only a very slight increase in Cmax, in EM subjects, was observed in the combination treatment when compared to monotherapy.
Table 1.6: Percent (%) Increase in Pharmacokinetic Parameters (Cmax and AUC0-12) for Extensive Metabolizers (EM) and Poor Metabolizers (PM) During Combination Therapy† vs. Monotherapy††
| PHARMACOKINETIC PARAMETER | Active Substance | ||||
| rabeprazole | clarithromycin | clarithromycin M-5 metabolite (14-hydroxyclarithromycin) | amoxicillin | ||
| % Increase Cmax (μg/mL) | EM* | 38% | 11% | 45% | 11% |
| PM* | 22% | 24% | 67% | no interaction | |
% Increase AUC0-12 (μg·h/mL) | EM | 32% | 11% | 46% | no interaction |
| PM | 35% | 24% | 73% | no interaction | |
† Test treatment (combination therapy) consisted of clarithromycin 400 mg + amoxicillin 750 mg + rabeprazole 20 mg †† Reference treatments (monotherapy): A: clarithromycin 400 mg; B: amoxicillin 750 mg; C: rabeprazole 20 mg *EM = Extensive Metabolizer; PM = Poor Metabolizer
STORAGE AND STABILITY
Store at room temperature (15° to 25°C) protected from moisture.
DOSAGE FORMS, COMPOSITION AND PACKAGING
Abbott-Rabeprazole is available as delayed release tablets for oral administration.
Abbott-Rabeprazole 10 mg: Pink colored, round biconvex, delayed release tablets imprinted with '38' on one side in black ink and plain on other side; are available in HDPE bottles of 100 tablets.
Abbott-Rabeprazole 20 mg: Yellow colored, round biconvex, delayed release tablets imprinted with '107' on one side in black ink and plain on other side; are available in HDPE bottles of 100 tablets.
Composition
Each delayed release tablet contains:
Medicinal ingredient: 10 mg or 20 mg of rabeprazole sodium.
Non-medicinal Ingredients: Diethyl Phthalate, Ethyl Cellulose (7 cps), Ferric Oxide Red, Ferric Oxide Yellow, Hypromellose Phthalate, Mannitol, Magnesium Oxide, Magnesium Stearate, Povidone, Sodium Starch Glycolate, Talc, Titanium Dioxide and OPACODE monogramming ink S-1-17823 BLACK(Shellac glaze, iron oxide black and propylene glycol).
PART II: SCIENTIFIC INFORMATION
PHARMACEUTICAL INFORMATION
Drug Substance
Proper name: Rabeprazole sodium
Chemical name: 2-[[[4-(3-Methoxypropoxy)-3-methyl-2-pyridinyl]methyl]sulfinyl]-1H- benzimidazole Sodium
2-({[4-(3-Methoxypropoxy)-3-methyl-2-pyridyl]methyl}sulfinyl)-1H-benzimidazole Sodium
Molecular formula: C18H20N3NaO3S
Molecular mass: 381.4 g/mol
Structural formula:
Na
O CH3
O
CH3
S
N
N
N
O
Physicochemical properties:
Description: White to off - white powder.
Solubility: Soluble in water.
Aqueous solubility: The aqueous solubility of Rabeprazole Sodium as a function of pH at
37°C
| Medium | pH | Solubility in mg/ml | ||||||
| Water | 6.6 | 428.070 | ||||||
| Phosphate Buffer | 6.8 | 0.830 | ||||||
| Phosphate Buffer | 8.0 | 1.412 | ||||||
| Phosphate Buffer | 9.0 | 2.962 | ||||||
| Phosphate Buffer | 11.0 | 407.397 | ||||||
pH: 10 to 11 (1% w/v in water)
pKa: 4.53 and 17.33
Log P (octanol/water) : 0.6
CLINICAL TRIALS
Comparative Bioavailability Studies
A comparative oral bioavailability study was conducted as a Double Blind, Randomized, 2-Period, 2-Treatment, 2-Sequence, Crossover, Single-Dose study in fifty-six (56) healthy adult Asian male volunteers under fasting conditions. Forty-nine (49) volunteers completed both periods of the study and were included in the statistical analysis. The rate and extent of absorption of Rabeprazole were measured following oral administration of either Abbott-Rabeprazole Delayed Release Tablets 20 mg (Abbott Laboratories, Limited) or Pariet®20 mg Enteric Coated Tablets containing Rabeprazole Sodium (Janssen-Ortho Inc., Canada). The results from measured data are summarized in table 2.1:
Table 2.1
* Abbott-Rabeprazole Delayed Release Tablets 20 mg by Abbott Laboratories, Limited † PARIET® (rabeprazole sodium) 20 mg Enteric-Coated Tablet by Janssen-Ortho Inc. Canada, purchased in Canada § Expressed as the median (range) only
€ Expressed as the arithmetic mean (CV %) only
A comparative oral bioavailability study was conducted as a Double Blind, Randomized, 2-Period, 2-Treatment, 2-Sequcnce, Crossover, Single-Dose study in fifty-six (56) healthy adult Asian male volunteers under fed conditions. Fifty-four (54) volunteers completed both periods of study and were included in the statistical analysis. The rate and extent of absorption of Rabeprazole were measured following oral administration of either Abbott-Rabeprazole Delayed Release Tablets 20 mg (Abbott Laboratories, Limited) or Pariet®20 mg Enteric Coated Tablets containing Rabeprazole sodium (Janssen-Ortho Inc., Canada). The results from measured data are summarized in table 2.2:
| Rabeprazole | |||||||||
| (1 x 20 mg) | |||||||||
| From measured data | |||||||||
| Geometric Mean | |||||||||
| Arithmetic Mean (CV %) | |||||||||
| Parameter | Test* | Reference† | % Ratio of | 90% | |||||
| Geometric | Confidence | ||||||||
| Means | Interval | ||||||||
AUCT (ng.hr/ml) | 841.5 984.0 (59.2) | 809.5 982.0 (64.3) | 103.9 | 91.8-117.6 | |||||
AUCI (ng.hr/ml) | 853.3 996.7 (59.3) | 841.3 1006.2 (62.9) | 101.3 | 91.6-112.2 | |||||
Cmax (ng/ml) | 405.3 473.7 (50.5) | 395.2 500.8 (58.6) | 102.7 | 81.6-129.3 | |||||
| §Tmax (hr) | 4.0 (2.0-9.0) | 3.3 (2.0-9.0) | |||||||
| €T 1/2 (hr) | 2.3 (82.3) | 3.0 (152.1) | |||||||
Table 2.2
| Rabeprazole | |||||||||
| (1 x 20 mg) | |||||||||
| From measured data | |||||||||
| Geometric Mean | |||||||||
| Arithmetic Mean (CV %) | |||||||||
| Parameter | Test* | Reference† | % Ratio of | 90% | |||||
| Geometric | Confidence | ||||||||
| Means | Interval | ||||||||
AUCT (ng.hr/ml) | 1235.1 1412.0 (48.9) | 1220.6 1370.0(48) | 101.2 | 94.2-108.6 | |||||
AUCI (ng.hr/ml) | 1273.4 1442.8 (47.8)# | 1230.5 1380.8 (48.1) | 102.5# | 95.8-109.7# | |||||
Cmax (ng/ml) | 723.1 801.3 (38.5) | 698.6 773.7 (36.5) | 103.5 | 90.5-118.4 | |||||
| § Tmax (hr) | 6.3(2.0-24.0) | 6.3 (2.0-24.0) | |||||||
| €T ½ (hr) | 2.1 (61.3) # | 2.4 (160.2) | |||||||
* Abbott-Rabeprazole Delayed Release Tablets 20 mg by Abbott Laboratories, Limited
† PARIET® (rabeprazole sodium) 20 mg Enteric-Coated Tablet by Janssen-Ortho Inc. Canada, purchased in Canada § Expressed as the median (range) only
€ Expressed as the arithmetic mean (CV %) only
# N= 53
Study results
Healing of Erosive or Ulcerative Gastroesophageal Reflux Disease (GERD) In a U.S. multicentre, double-blind, placebo-controlled study, 103 patients were treated for up to eight weeks with placebo, 10 mg, 20 mg or 40 mg rabeprazole QD. For this and all studies of GERD healing, only patients with GERD symptoms and at least grade 2 esophagitis (modified Hetzel-Dent grading scale) were eligible for entry. Endoscopic healing was defined as grade 0 or
- 1. Each active dose was significantly superior to placebo in producing endoscopic healing after four and eight weeks of treatment. The percentage of patients with endoscopic healing with 20 mg rabeprazole dosing and placebo are presented in Table 2.3.
Table 2.3: Healing of Erosive or Ulcerative Gastroesophageal Reflux Disease (GERD) Percentage of Patients Healed
| Week | 20 mg Rabeprazole QD | Placebo |
| 4 8 | N=25 56%* 84%* | N=26 0% 12% |
* p<0.001 vs. placebo
A 20 mg Rabeprazole dose QD was also significantly more effective than placebo in providing complete resolution of heartburn frequency (p=0.003), in providing complete resolution of daytime heartburn severity (p=0.036), and in decreasing the amount of antacid taken per day (p<0.001).
In a U.S. multicentre, double-blind, active-controlled study of 338 patients, rabeprazole was statistically superior to ranitidine with respect to the percentage of patients healed at endoscopy after four and eight weeks of treatment (see Table 2.4).
Table 2.4: Healing of Erosive or Ulcerative Gastroesophageal Reflux Disease (GERD) Percentage of Patients Healed
| Week | Rabeprazole 20 mg QD | Ranitidine 150 mg QID |
| 4 8 | N=169 59%* 87%* | N=169 36% 66% |
* p<0.001 vs. ranitidine
A 20 mg rabeprazole dose QD was also significantly more effective than ranitidine 150 mg QID in providing complete resolution of heartburn frequency (p<0.001) and daytime (p=0.025) and nighttime (p=0.002) heartburn severity.
In an international, double-blind, active-controlled study of 202 patients treated with a 20 mg rabeprazole dose QD or 20 mg omeprazole QD for up to eight weeks, rabeprazole was comparable to omeprazole in producing endoscopic healing. The percentage of patients healed at endoscopy at four and eight weeks are given in Table 2.5.
Table 2.5: Healing of Erosive or Ulcerative Gastroesophageal Reflux Disease (GERD) Percentage of Patients Healed
| Week | Rabeprazole 20 mg QD | Omeprazole 20 mg QD |
| 4 8 | N=100 81%* 92%* | N=102 81% 94% |
Additionally, a 20 mg rabeprazole dose QD was as effective as omeprazole 20 mg in reducing heartburn frequency, improving daytime and nighttime heartburn severity, and reducing the amount of antacid taken per day.
Long-term Maintenance of Healing of Erosive or Ulcerative Gastroesophageal Reflux Disease (GERD Maintenance)
The long-term maintenance of healing in patients with erosive or ulcerative GERD previously healed with gastric antisecretory therapy was assessed in two U.S. multicentre, double-blind, placebo-controlled studies of 52 weeks’ duration. Two studies of identical design randomized 209 and 288 patients, respectively, to receive either a 10 mg or 20 mg of rabeprazole dose QD or placebo. In both studies, rabeprazole was significantly superior to placebo in the maintenance of GERD healing. Table 2.6 gives results from a combined analysis of the two studies for the percentages of patients with endoscopically maintained healing.
Table 2.6: Long-term Maintenance of Healing of Erosive or Ulcerative Gastroesophageal Reflux Disease (GERD Maintenance) - Percentage of Patients in Endoscopic Remission
| Week | rabeprazole 10 mg QD | rabeprazole 20 mg QD | Placebo |
| N=159 | N=160 | N=169 | |
| 4 | 87%* | 94%*† | 42% |
| 13 | 83%* | 92%*† | 36% |
| 26 | 82%* | 91%*† | 31% |
| 39 | 81%* | 89%*† | 30% |
| 52 | 75%* | 87%*† | 29% |
*(p<0.0001) vs. placebo
†(p<0.05) vs. rabeprazole 10 mg QD
In both multicentre trials, rabeprazole 20 mg QD was significantly more effective than placebo in preventing recurrence of heartburn frequency (p<0.001) as well as daytime (p<0.001) and nighttime (p≤0.003) heartburn severity.
Symptomatic Gastroesophageal Reflux Disease (GERD)
Two U.S. multicentre, double-blind, placebo-controlled studies were conducted in 316 patients with daytime and nighttime heartburn. Patients reported 5 or more periods of moderate to very severe heartburn during the placebo treatment phase the week prior to randomization. Patients were confirmed by endoscopy to have no esophageal erosions. Patients enrolled did not have a history of esophagitis. Patients entering the trial were required, at a minimum, not to have taken any proton pump inhibitor (PPI) within the 14 days before study entry, allowing time for the development of mucosal evidence of disease in those patients with true esophagitis.
From the combined data from these two studies, there was a significantly greater (p<0.001) proportion of heartburn-free periods for the rabeprazole 10 mg group (53%) and the rabeprazole 20 mg group (49%) when compared to placebo (25%) over the 4-week treatment duration. The rabeprazole 10 and 20 mg groups also significantly reduced daily antacid consumption versus placebo over 4 weeks (p<0.001). Results on the proportion of subjects with complete heartburn relief and satisfactory relief of heartburn from the two pivotal clinical trials are summarized in Tables 2.7 and 2.8 below.
Table 2.7: Complete Relief of Heartburn and Satisfactory Relief of Heartburn Frequency from Study RAB-USA-2
| PLACEBO n (%)† | Rabeprazole 10 mg QD n (%)† | Rabeprazole 20 mg QD n (%)† | |
| Intent-To-Treat (ITT) population | N=68 | N=64 | N=67 |
| Per-Protocol (PP) population | N=61 | N=59 | N=58 |
| Complete Heartburn Relief Double-blind Week 2 Double-blind Week 4 | 0 (0.0) 2 (2.9) | 12 (18.8) 17 (26.6) | 12 (17.9) 17 (25.4) |
| Satisfactory Heartburn Relief Double-blind Week 2 Double-blind Week 4 | 12 (17.6) 19 (27.9) | 40 (62.5) 33 (51.6) | 29 (43.3) 34 (50.7) |
† Analysis based on ITT population
Table 2.8: Complete Relief of Heartburn and Satisfactory Relief of Heartburn Frequency from Study RAB-USA-3
| PLACEBO n (%)† | Rabeprazole 20 mg QD n (%)† | |
| Intent-To-Treat (ITT) population | N=58 | N=59 |
| Per-Protocol (PP) population | N=45 | N=45 |
| Complete Heartburn Relief Double-blind Week 2 Double-blind Week 4 | 2 (3.4) 2 (3.4) | 13 (22.0) 17 (28.8) |
| Satisfactory Heartburn Relief Double-blind Week 2 Double-blind Week 4 | 15 (25.9) 12 (20.7) | 33 (55.9) 30 (50.8) |
† Analysis based on ITT population
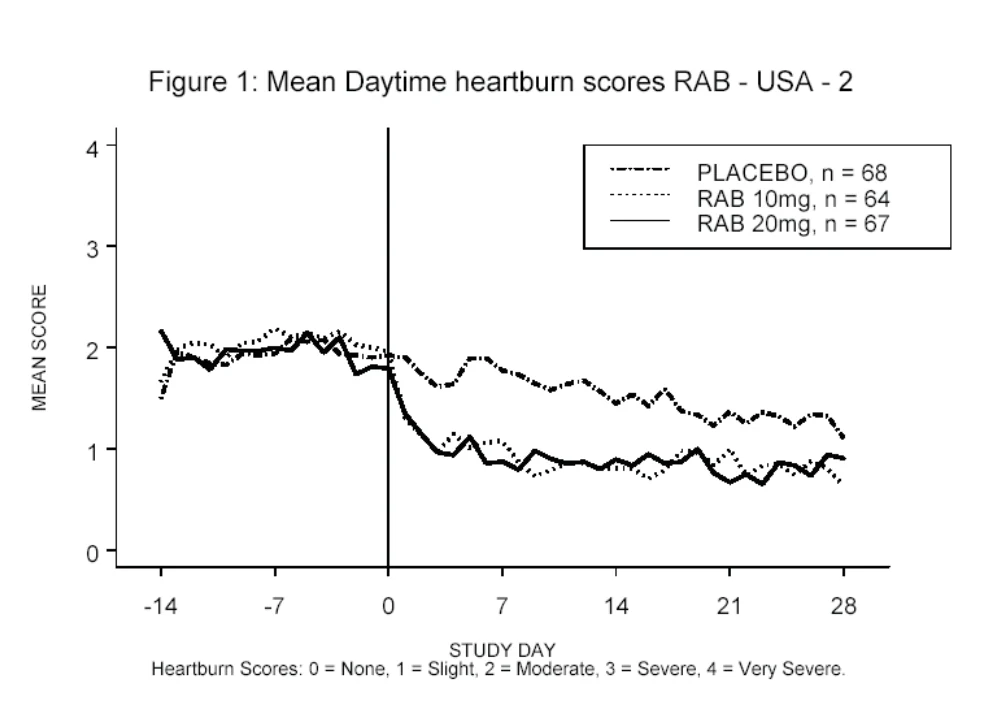
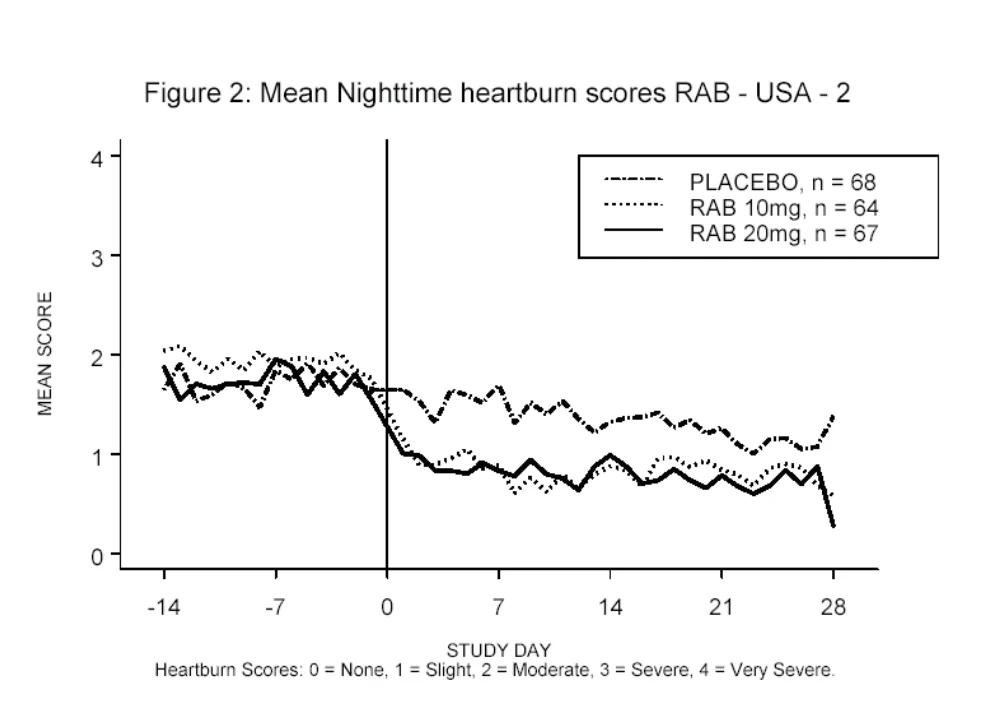
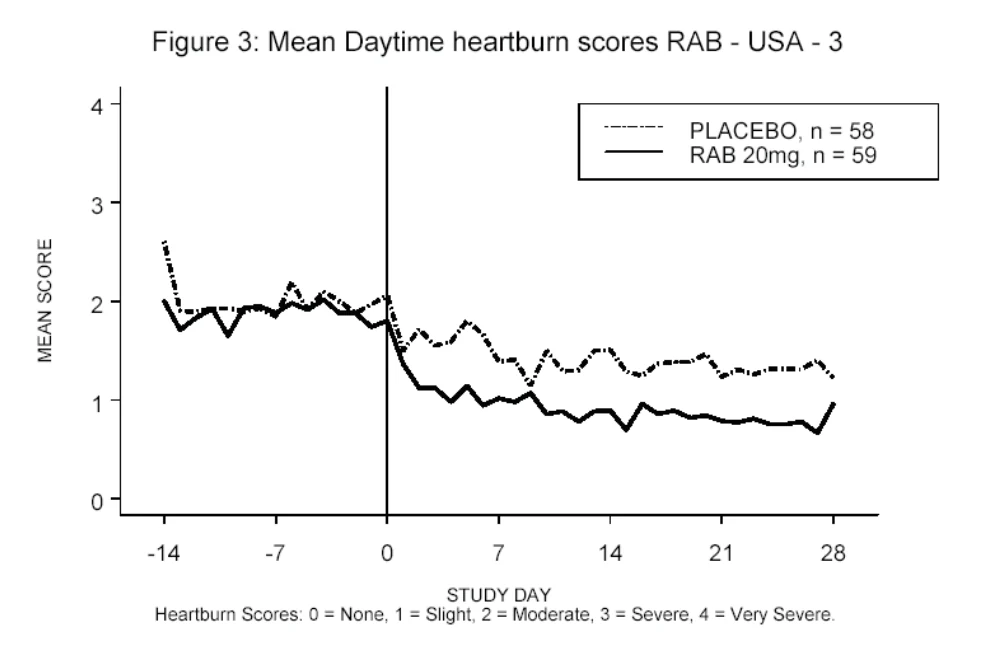
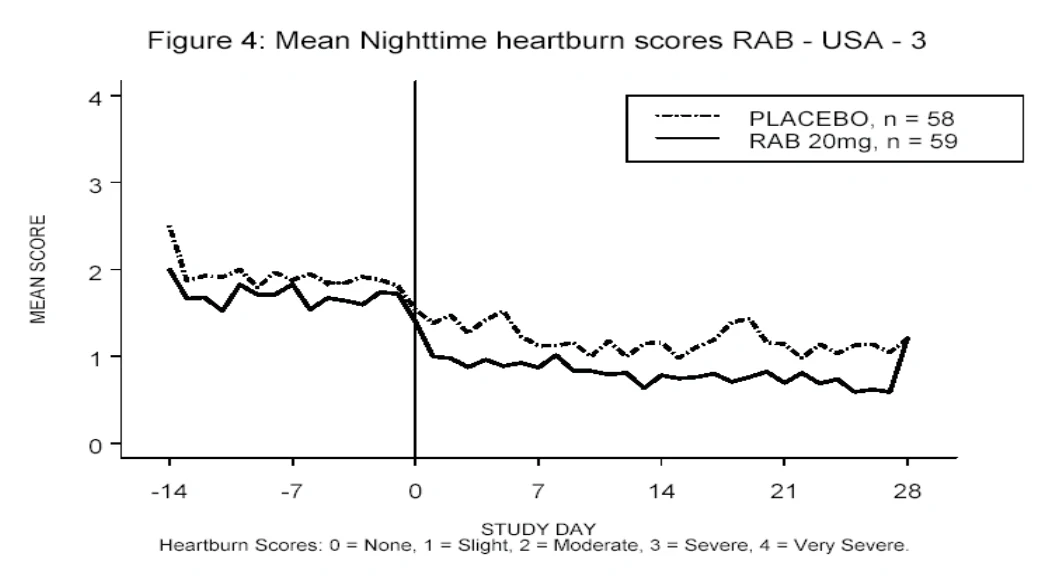
The mean decreases from baseline in average daytime and nighttime heartburn scores were significantly greater for rabeprazole 20 mg as compared to placebo at week 4. Graphical displays depicting the daily mean daytime and nighttime scores are provided in Figures 1 to 4.
Healing of Duodenal Ulcers
In a U.S. double-blind, multicentre study assessing the effectiveness of 20 mg and 40 mg rabeprazole dosages QD versus placebo for healing endoscopically defined duodenal ulcers, 100 patients were treated for up to four weeks. Rabeprazole was significantly superior to placebo in producing healing of duodenal ulcers. The percentages of patients with endoscopic healing are presented in Table 2.9.
Table 2.9: Healing of Duodenal Ulcers Percentage of Patients Healed
| Week | Rabeprazole 20 mg QD | Placebo |
| N=34 | N=33 | |
| 2 | 44% | 21% |
| 4 | 79%* | 39% |
* p=0.001 vs. placebo
Patients treated with a rabeprazole dosage of 20 mg QD reported significantly less ulcer pain frequency (p<0.001) and significantly less daytime (p=0.002) and nighttime (p=0.001) ulcer pain severity than patients treated with placebo. Additionally, rabeprazole 20 mg QD was significantly more effective than placebo in reducing daily antacid use (p<0.001).
In a U.S. multicentre, double-blind, active-controlled trial, 376 patients with endoscopically defined duodenal ulcers were treated with a 20 mg rabeprazole dose QD or ranitidine 150 mg BID for up to four weeks. The percentages of patients with endoscopic healing at two and four weeks are presented in Table 2.10.
Table 2.10: Healing of Duodenal Ulcers Percentage of Patients Healed
| Week | Rabeprazole 20 mg QD | Ranitidine 150 mg BID |
| N=188 | N=188 | |
| 2 | 40%* | 26% |
| 4 | 83%+ | 73% |
* p=0.002 vs. ranitidine
+ p=0.017 vs. ranitidine
Additionally, Rabeprazole 20 mg QD was significantly more effective than ranitidine 150 mg BID in producing complete resolution of ulcer pain frequency (week 2, p=0.006), in alleviating night time ulcer pain severity (week 2, p=0.044), and in reducing antacid consumption (p=0.037).
An international double-blind, active-controlled trial was conducted in 205 patients comparing 20 mg Rabeprazole QD with 20 mg omeprazole QD. In patients with endoscopically defined duodenal ulcers treated for up to four weeks, Rabeprazole was comparable to omeprazole in producing healing of duodenal ulcers. The percentages of patients with endoscopic healing at two and four weeks are presented in Table 2.11.
Table 2.11: Healing of Duodenal Ulcers Percentage of Patients Healed
| Week | Rabeprazole 20 mg QD | Omeprazole 20 mg QD |
| N=102 | N=103 | |
| 2 | 69% | 61% |
| 4 | 98% | 93% |
Additionally, Rabeprazole 20mg QD was significantly (p=0.038) more effective than omeprazole 20 mg in reducing daytime ulcer pain severity at week four.
Healing of Gastric Ulcers
In a U.S. double-blind, multicentre study assessing the effectiveness of a 20 mg and 40 mg Rabeprazole dosage QD versus placebo for healing endoscopically defined gastric ulcers, 94 patients were treated for up to six weeks. Rabeprazole was significantly superior to placebo in producing healing of gastric ulcers. The percentages of patients with endoscopic healing at three and six weeks are presented in Table 2.12.
Table 2.12: Healing of Gastric Ulcers Percentage of Patients Healed
| Week | Rabeprazole 20 mg QD | Placebo |
| N=32 | N=31 | |
| 3 | 32% | 29% |
| 6 | 90%* | 39% |
* p<0.001 vs. placebo
Patients treated with a 20 mg Rabeprazole dose QD for six weeks also required significantly fewer daily antacid doses than did patients treated with placebo (p=0.039).
In two active-controlled trials of Rabeprazole, one conducted in the U.S. versus ranitidine 150 mg BID and one conducted in Europe versus omeprazole 20 mg, the rates of endoscopic healing of gastric ulcers were the same with the two treatments at three weeks and at six weeks.
In the European study comparing a Rabeprazole 20 mg dose QD to omeprazole 20 mg, Rabeprazole was significantly superior in reducing ulcer pain frequency (week 6, p=0.006), in improving daytime ulcer pain severity (week 3, p=0.023), and in providing complete resolution of nighttime ulcer pain severity (week 6, p=0.022).
H. pylori Eradication
The U. S. multicentre Study 604 was a double-blind, parallel-group comparison of rabeprazole, amoxicillin, and clarithromycin for 3, 7, or 10 days vs. omeprazole, amoxicillin and clarithromycin for 10 days. In this study, patients with H. pylori infection were stratified 1:1 so that half the patients had peptic ulcer disease and half did not. Therapy consisted of rabeprazole 20 mg, amoxicillin 1000 mg, and clarithromycin 500 mg, all two times daily (RAC) or omeprazole 20 mg, amoxicillin 1000 mg, and clarithromycin 500 mg, all two times daily (OAC). Results are under INDICATIONS AND CLINICAL USE section, Table 1.1. As measured by bacteriological response rate (i.e. the elimination of H. pylori), 7-day and 10-day RAC treatments were equivalent to the 10-day OAC treatment in both the Intent-to-Treat and Per-Protocol populations. In the Intent-to-Treat dataset, 7- and 10-day RAC therapy produced response rates of 77% and 78%, respectively, and the 10-day OAC therapy response rate was 73%. In the Per-Protocol subset, cure rates for 7-day and 10-day RAC and 10-day OAC therapies were, respectively, 84%, 86% and 82%. Eradication rates in the RAC 3-day regimen were lower and not equivalent to the other regimens. Table 1.1 shows that H. pylori eradication, defined as a negative 13C-UBT test at the ≥6-week post-treatment measurement, was equivalent for RAC 7 and 10 days and OAC 10-day treatment.
A high proportion of clarithromycin-susceptible H. pylori were eradicated by 7- and 10-day RAC therapy: 80% and 83% in the Intent-to-Treat dataset and 90% and 91% in the Per-Protocol subset. There is a low H. pylori eradication rate in patients with clarithromycin-resistant H. pylori isolates (see Table 2.14).
The European multicentre Study 603 was a double-blind, parallel-group comparison of rabeprazole and omeprazole triple therapy regimen (PPI, amoxicillin and clarithromycin) for 7 days for the eradication of H. pylori in subjects with documented Peptic Ulcer Disease. Therapy consisted of rabeprazole 20 mg, clarithromycin 500 mg, and amoxicillin 1000 mg, all twice daily, or omeprazole 20 mg, clarithromycin 500 mg and amoxicillin 1000 mg, all twice daily.
Successful eradication of H. pylori was defined as a negative 13C-UBT at both the Week 5 and Week 13 post-treatment assessment. The results of this study confirmed the efficacy of the RAC 7-day regimen in the eradication of H. pylori. In the Intent-to-Treat population, rabeprazole therapy (RAC) produced an eradication rate of 84%, and an eradication rate of 72% for omeprazole therapy (OAC). In the Per-Protocol population, the response rates for RAC and OAC therapies were 94% and 84%, respectively (see Table 1.1).
Treatment of Pathological Hypersecretory Conditions Including Zollinger-Ellison Syndrome Twelve patients with idiopathic gastric hypersecretion or Zollinger-Ellison syndrome have been treated successfully with rabeprazole doses from 20 to 120 mg for up to 12 months. Rabeprazole treatment produced satisfactory inhibition of gastric acid secretion in all patients and complete resolution of signs and symptoms of acid-peptic disease where present. Rabeprazole treatment also prevented recurrence of gastric hypersecretion and manifestations of acid-peptic disease in all patients. The high doses of rabeprazole used to treat this small cohort of patients with gastric hypersecretion were not associated with drug-related adverse effects.
DETAILED PHARMACOLOGY
Animal Pharmacology
Effects on Gastric Acid Secretion
Rabeprazole sodium was shown to be a potent inhibitor of gastric acid secretion under basal and histamine-stimulated conditions in rats and dogs. The inhibitory effect of rabeprazole sodium on gastric acid secretion was more marked under hyperacidic conditions than on basal acid secretion. The ED50 values for rabeprazole sodium on gastric acid secretion are summarized in Table 2.13, below.
Table 2.13: Rabeprazole Sodium ED50 Value for the Inhibition of Gastric Acid Secretion
| Species | Model | Acid Secretion | ED50 (mg/kg) |
| rat | pylorus ligated | basal | 3.4 |
| rat | pylorus ligated | basal | ca. 3 |
| rat | pylorus ligated | histamine-stimulated | ca. 1 |
| rat | acute gastric fistula | histamine-stimulated | Ca. 1.4 |
| dog | chronic gastric fistula | histamine-stimulated | 0.06 |
Anti-Ulcer Effects
Rabeprazole sodium was shown to have significant anti-ulcer effects in several ulcerogenic models: HCl-ethanol-induced ulcers, water-immersion restraint stress-induced ulcers, cold-restraint stress induced ulcers, or cysteamine-induced duodenal ulcers, acetic acid-induced ulcers, and Shay ulcers in rats. The available ED50 values for rabeprazole sodium on the anti-ulcer activity are summarized in Table 2.14.
Table 2.14: Rabeprazole Sodium ED50 Value for the Anti-Ulcer Effect
| Species | Ulcerogenesis Model | ED50 (mg/kg) |
| rat | HCl-ethanol-induced | ca. 17 |
| rat | water-immersion restraint stress-induced | ca. 3.9 |
| rat | cold-restraint stress ulcer | ca. 3.5 |
Similar potency was observed for rabeprazole sodium on gastric acid secretion inhibition, except in the severe ulcer model induced with hydrochloric acid and ethanol.
Duration of the Antisecretory Effect
In conscious dogs with indwelling gastric fistulas, the duration of the antisecretory action following a single intraduodenal dose of rabeprazole sodium or omeprazole after histamine challenges or pentagastrin challenges appeared to be dose-related and was longer in omeprazole-treated animals than rabeprazole sodium-treated animals within 24 hours. The inhibitory effect on gastric acid secretion was not cumulative when either drug was used and there was no measurable drug effect three days after discontinuation of rabeprazole sodium as reflected by plasma gastrin levels.
Inhibitory Effects of Rabeprazole Sodium Metabolites on Gastric Acid Secretion The desmethyl (M-3) and the thioether (M-1) metabolites of rabeprazole sodium were both shown to inhibit histamine-stimulated gastric acid secretion in dogs with indwelling gastric fistulas but these activities were less potent than rabeprazole sodium.
A series of studies was conducted to determine the effects of rabeprazole sodium on H+, K+-ATPase activity.
Using three experimental systems, the mechanism(s) by which gastric acid secretion returned to normal levels following irreversible inhibition of the proton pump (H+, K+-ATPase) by rabeprazole sodium was investigated. New synthesis of H+, K+-ATPase and the dissociation of the enzyme inhibitor complex by endogenous extracellular GSH are suggested as contributing to the reversal of the antisecretory activity in dogs.
Anti-Ulcer Effects
Rabeprazole sodium had no inhibitory effect on lesion healing or collagen regeneration in ethanol-HCl-induced ulcers in rats, whereas histamine H2-receptor antagonists (cimetidine and famotidine) had inhibitory effects on lesion healing and collagen synthesis.
Gastrointestinal Studies
Rabeprazole sodium had no significant effect on gastric emptying or intestinal transit in mice at doses of 1, 3, 10 or 30 mg/kg. No clear or significant effects on gastric or duodenal motility were observed after rabeprazole sodium was administered (i.d.) at 50 mg/kg. At 100 mg/kg (i.d.), rabeprazole sodium reduced gastric motility for 40 to 60 minutes, and a dose of 200 mg/kg (i.d.) rabeprazole sodium reduced gastric motility for up to 90 minutes. Rabeprazole sodium had no significant effect on biliary or pancreatic secretion in anesthetized rats.
Pharmacokinetics
Absorption and Pharmacokinetics
Rabeprazole sodium is unstable in acidic media and undergoes pH-dependent decomposition especially rapidly below pH 4-5. When administered orally in an unbuffered solution, rabeprazole sodium is absorbed rapidly by the mouse, rat, rabbit and dog, but its bioavailability is low at gastric pH. Protection against gastric acid either by oral administration in sodium bicarbonate buffer (rodents and dog), by pretreatment with aqueous sodium bicarbonate (rat, dog), restricted feeding regimen (rat, dog), or by delivery directly (rat) or indirectly as enteric-coated tablets (dog, long-term studies) into the duodenum, increased rabeprazole sodium bioavailability. By contrast, pretreatment with pentagastrin (i.m.), which stimulates gastric acid secretion, significantly lowered canine Cmax and AUC values for orally administered rabeprazole sodium.
Stereochemical Pharmacokinetic Considerations
The R(+) and S(-) enantiomers of rabeprazole sodium exhibited stereochemically related pharmacokinetic differences when administered individually either p.o. (1.5 mg/kg, in water) or i.v. (1.5 mg/kg, in saline) to the Beagle dog. The same differences were seen after co-
administration of the RS-(") racemate, both p.o. and i.v. (3 mg/kg). With similar apparent volumes of distribution, the systemic clearance, Cltot, of R(+)-rabeprazole sodium was approximately half that of S(-)-rabeprazole sodium, and the ratio both of plasma half-lives and AUC values after i.v. administration was approximately 2.0. The shorter half-life and greater clearance of the S(-) enantiomer is probably due to more rapid metabolism, as evidenced by much higher plasma concentrations of the sulphone metabolite M-2 after S(-)-rabeprazole sodium administration. There was little or no interconversion between enantiomers in vivo.
In the rat, co-administration of both enantiomers of rabeprazole sodium as the RS (") racemate (40 mg/kg, i.v.) produced pharmacokinetic results comparable to those when R(+)-rabeprazole sodium and S(-)-rabeprazole sodium were administered separately (20 mg/kg, i.v.). The R/S ratios for AUC value, total clearance, and volume of distribution were, respectively, 1.34, 0.67, and 0.62. Plasma half-lives for R(+)- and S(-)-rabeprazole sodium were comparable and the principal plasma metabolites were the achiral thioether (M-1) and desmethyl thioether (M-3). The greater volume of distribution for the S(-) enantiomer is consistent with lower protein binding relative to R(+)-rabeprazole sodium.
Protein Binding and Erythrocyte Penetration
Species-specific differences in protein binding of racemic rabeprazole and its individual enantiomers were seen in human, rat and Beagle dog plasma in vitro. There was no difference in the binding of the individual enantiomers in human and dog plasma, but the S(-) isomer was significantly less protein-bound than the R(+) form in rat plasma. Ex vivo, protein binding of radioactivity after oral administration of 14C-rabeprazole sodium was lower in the dog and rat, and decreased as a function of time post-dose, reflecting weaker binding of metabolites present to a greater extent than rabeprazole sodium in vivo. In vitro, 14C-rabeprazole penetrated erythrocytes rapidly and to a much smaller extent in human and canine blood than in rat blood.
Tissue Distribution
Distribution of radioactivity into tissues was determined after oral administration of 14C-E3810, 10 mg/kg, to the Beagle dog. With the exception of the thyroid and pigmented ocular structure (ciliary body > iris >> choroid body), tissue depletion of radioactivity paralleled that in plasma and had fallen to <0.2 μg-equiv/g by Day 28. In another study, tissue distribution was similar after p.o. and i.v. administration, and radioactivity in excess of that in plasma persisted in thyroid, choroid, and to a lesser extent, in lens and retina 8 days post-dose. Radioactivity in gastric mucosa 0.5 hours after i.v. administration was two times higher than in plasma. Pretreatment with pentagastrin resulted in higher levels of radioactivity in gastric mucosa in the dog. High intracellular radioactivity was localized in the 105,000 x g pellet of gastric mucosal cell homogenates, the locus for intracellular binding of E3810 (H+K+-ATPase).
After intraduodenal administration of 14C-rabeprazole to the rat, 20 mg/kg, plasma and tissue clearance was rapid except for hematocytes, thyroid, spleen, adrenals and liver, in which drug-related materials persisted at levels in excess of that in plasma nine days post-dose.
Tissue distribution profiles of rabeprazole-related substances were investigated by administering 20 mg/kg of 14C-rabeprazole intraduodenally to male rats. Identification of metabolites in tissues
revealed that M-5 and M-6 (the mercapturic acid and carboxylic acid analogs, respectively) were the major metabolites in all tissues except the stomach where M-1 (the thioether of E3810) predominated.
One hour after i.v. administration of a 5 mg/kg dose of 14C-rabeprazole to SD rats, the highest levels of 14C were observed in the gastric mucosa, followed in descending order by glandular stomach, kidney, bladder, liver, hematocytes, small intestine and thyroid. The highest levels of 14C-rabeprazole after 168 hours were found in hematocytes.
Similar patterns of tissue distribution of radioactivity, depletion kinetics, and metabolic profile of 14C-E3810 were observed after single intraduodenal (20 mg/kg) and 14-day repeated oral (10 mg/kg/day) dosing.
Following a single oral dose of 14C-rabeprazole, 20 mg/kg, to pregnant rats on Days 12 and 19 of gestation, the highest concentrations of radioactivity in the tissues of dams (excluding the gastrointestinal tract) were found in the liver and kidney. By 24 hours post-dose, the radioactivity in all tissues, except stomach and thyroid, had declined. No substantial accumulation of 14C-rabeprazole (0.01% to 1.16% of administered dose) was observed in fetal tissues after administration of 14C-rabeprazole to pregnant rats on Days 12 or 19 of gestation. Significant levels of radioactivity (two- to seven-fold higher levels than in blood) were observed in milk (obtained from the stomach of neonates) after the oral administration of 14C-rabeprazole to lactating females on the 14th day after delivery.
Human Pharmacology
Pharmacodynamics and Helicobacter pylori Status
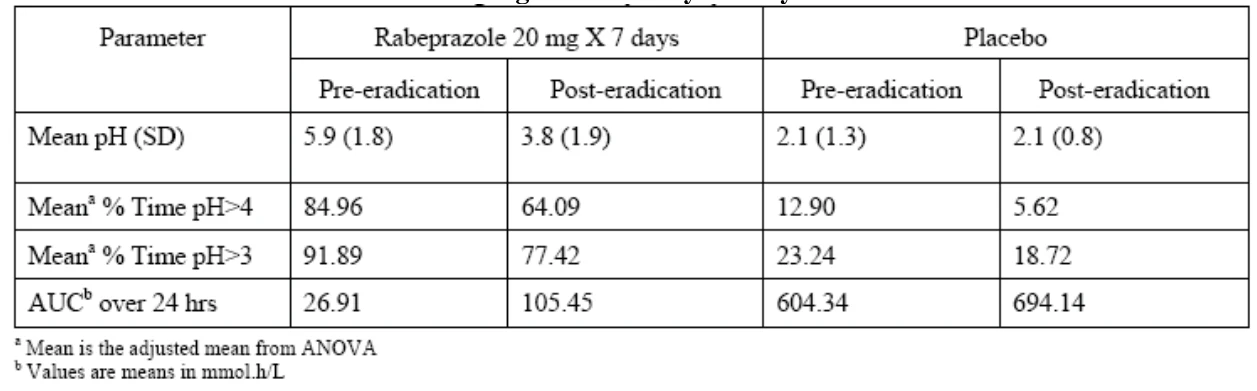
Twenty-four healthy volunteers (14 males and 10 females), who had an H. pylori positive status as assessed by serology and 13C-Urea Breath Test (13C-UBT), received ranitidine bismuth citrate, tetracycline, and clarithromycin therapy for the eradication of H. pylori. The eradication session was followed by a four-week therapy-free period, after which rabeprazole, omeprazole, lansoprazole and placebo were administered in a crossover design. The effect of eradication of H. pylori on the 24-hour intragastric acidity and plasma gastrin concentration were then assessed. Presented in Table 2.15 below are the placebo and rabeprazole data.
Table 2.15: Test Results of 24-hour Intragastric Acidity on Day 7 - Intent to Treat
MICROBIOLOGY
Helicobacter pylori
Susceptibility testing of H. pylori isolates was performed for amoxicillin and clarithromycin using agar dilution methodology, and minimum inhibitory concentrations (MICs) were determined.
Incidence of Antibiotic-Resistant Organisms Among Clinical Isolates
Pretreatment Resistance: Clarithromycin pretreatment resistance rate (MIC ≥ 1 μg/mL) to H. pylori was 9% (51/560) at baseline in all treatment groups combined. A total of > 99% (558/ 560) of patients had H. pylori isolates which were considered to be susceptible (MIC ≤ 0.25 μg/ mL) to amoxicillin at baseline. Two patients had baseline H. pylori isolates with an amoxicillin MIC of 0.5 μg/ mL.
Clarithromycin Susceptibility Test Results and Clinical/Bacteriologic Outcomes: For the U. S. multicentre Study 604, the baseline H. pylori clarithromycin susceptibility results and the H. pylori eradication results post-treatment with 7- and 10-day 20 mg rabeprazole sodium, 1000 mg amoxicillin, 500 mg clarithromycin (RAC) therapy are shown in Table 2.16 below.
Table 2.16: Clarithromycin Susceptibility Test Results and Clinical/Bacteriologic Outcomesa for Triple Therapy -Intent to Treat
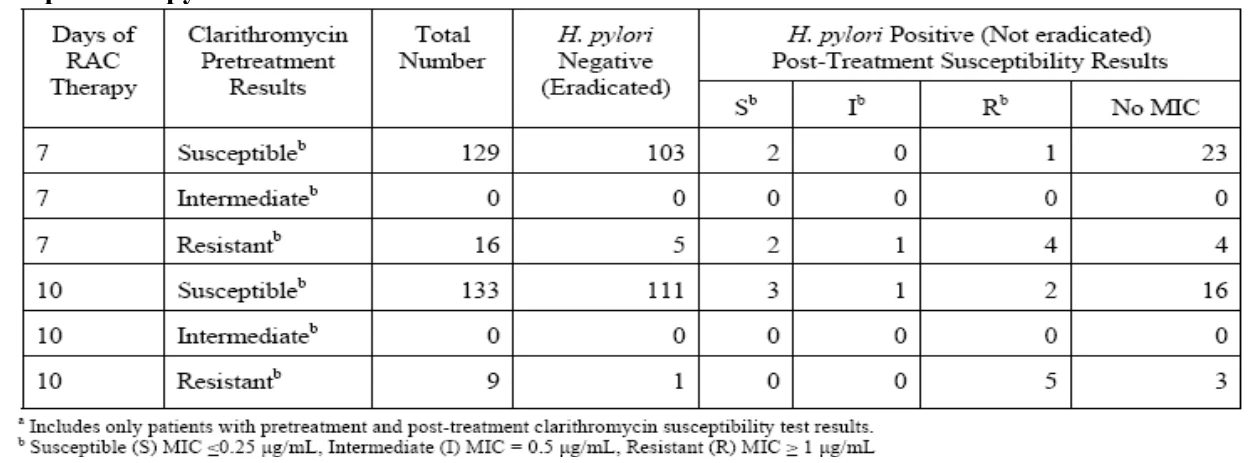
Patients not eradicated of H. pylori following rabeprazole/amoxicillin/clarithromycin triple therapy may have clarithromycin-resistant clinical isolates. Clarithromycin susceptibility testing should be done when possible. Patients with clarithromycin-resistant H. pylori should not be re-treated with a clarithromycin-containing regimen.
Amoxicillin Susceptibility Test Results and Clinical/Bacteriologic Outcomes: In the U.S. multicentre Study 604, a total of > 99% (558/560) of patients had H. pylori isolates which were considered to be susceptible (MIC ≤ 0.25 μg/mL) to amoxicillin at baseline. The other 2 patients had baseline H.pylori isolates with an amoxicillin MIC of 0.5 μg/mL, and both isolates were clarithromycin-resistant at baseline; in one case the H. pylori was eradicated. In the 7- and 10-day treatment groups, respectively, 75% (107/145) and 79% (112/142) of the patients who had pretreatment amoxicillin susceptible MICs (≤ 0.25 μg/mL) were eradicated of H. pylori. No patients developed amoxicillin resistant H. pylori during therapy.
Rabeprazole activity against H. pylori: As a single agent, rabeprazole demonstrates in vitro activity against H. pylori. The MIC range was 0.4 to 3.1 μg/mL against 15 isolates; the MIC50 was 1.6 and the MIC90 was 3.1 μg/mL.
TOXICOLOGY
Acute (Single-Dose) Toxicity Studies
Single-dose toxicity studies of rabeprazole and its metabolites, synthetic by-products, degradation products, and enantiomers were conducted in mice, rats and/or dogs (see Table 2.17).
The oral LD50 in mice and rats was ≥1000 mg/kg; the intravenous LD50 in mice and rats was ≥150 mg/kg. Clinical signs consisted of laboured breathing, prostration, salivation, mydriasis, convulsions, and death. In dogs, the oral lethal dose was > 2000 mg/kg. Clinical signs at oral
doses of 400 and 2000 mg/kg included watery diarrhea, tonic convulsions, emesis, salivation, and prostration. There was no delayed toxicity in these acute studies.
Table 2.17: List of Acute (Single-Dose) Toxicity Studies
Species/ Strain (Status) | Number/ Gender/ Group | Route of Admin./ Vehicle | Dose | Duration | LD50 or NOEL | |
| M | F | |||||
Mouse/ICR (Oral route: fasted 19
dosing; i. v. route: ad libitum feeding | 5 per sex per group | p.o. (gavage)/ purified water i.v./ physiological saline | Male: 629, 786, 983, 1229, 1536, 1920, and 2400mg/kg Female: 629, 786, 983, 1229, 1536, 1920, 2400 and 3000 mg/kg Male: 131, 164, 205, 256, and 320 mg/kg Female: 164, 205, 229, 256, and 320 mg/kg | Single dose | 1206 220 | 1012 237 |
Rat/ Slc: SD (oral route: fasted 17 - 24 hrs prior to dosing; i.v. route: ad libitum feeding) | 5 per sex per group | p.o. (gavage)/ purified water i.v./ physiological saline | Male: 819, 1024, 1280, 1431, 1600, and 2000 mg/kg Female: 655, 819, 1024, 1280, 1600, and 2000 mg/kg Male: 98, 123, 154, 172, and 192 mg/kg Female: 98, 123, 154, 192, 240, and 300 mg/kg | Single dose | 1447 157 | 1322 152 |
| Rat Slc: SD (ad libitum feeding) | 5 per sex per group | i.v./ NaOH and physiological saline | 0, 50, 100, and 200 mg (S-) E3810*/kg 50, 100, and 200 mg (R+) E3810*/kg | Single dose | Not Determined | Not Determined |
Rat/ Slc: SD (animals were fasted over night) | 5 per sex per group | Degradation Products I and II and Impurity p.o. (gavage) Metabolite i.v./ 0.5 methylcellulose solution | Degradation Prod. I : 0, 500, and 1500 mg/kg Degradation Prod. II: 50, 150, and 500 mg/kg Impurity: 500 and 1500 mg/kg Metabolite: 0, 10, 30 mg/kg (male and female), 100 mg/kg (male only) | Single dose | Not Determined | Not Determined |
| Dog/Beagle (ad libitum feeding) | 1 per sex per group | p.o (gavage)/ purified water | 80, 400, and 2000 mg/kg | Single dose | > 2000 | > 2000 |
* Rabeprazole sodium
Long-Term (Repeat-Dose) Toxicity Studies
Long-term toxicity of rabeprazole sodium was studied in mice, rats and dogs after oral and intravenous administration. Mice received oral doses of 2-400 mg/kg for up to 104 weeks. Rats received oral doses ranging from 1-300 mg/kg for up to 13 weeks and intravenous doses 1-75 mg/kg up to four weeks. Dogs received oral doses 0.1-30 mg/kg up to one year and intravenous doses 1-25 mg/kg up to 14 days.
Mouse
In mice, signs of toxicity (most evident in male mice) at 400 mg/kg included torpor, ataxia, hypopnea, bradypnea, and prostration. These signs resolved within 30 minutes. Increases in stomach and/or liver weight, thickening of the gastric glandular mucosa and/or hyperplastic gastropathy were observed at doses of 25, 100 and 400 mg/kg. It was concluded that oral doses up to 200 mg/kg (dose reduced to 100 mg/kg at week 41) for 88 weeks in males and l04 weeks in females did not provide any evidence of an oncogenic potential. A number of changes in the stomach that were attributable to the pharmacological activity of rabeprazole sodium were seen in animals treated with 200 mg/kg (dose reduced to 100 mg/kg at week 41).
Rat
In the rat, rabeprazole sodium was well tolerated in all dose groups (5, 15, 30, 60 and 120 mg/kg [females only]) when administered by gavage for six months, as morphologic changes were slight in magnitude and were not associated with alterations in growth, morbidity or mortality. Drug-related changes were detected in the kidney, thymus, stomach and/or thyroid at doses > 15 mg/kg. No effects were observed at 5 mg/kg.
In a 52-week study of rats administered doses of 1, 5 and 25 mg/kg by gavage, the gastric changes observed in the treated animals were attributable to the expected pharmacological effects and not toxicological changes, and the NOAEL was 5 mg/kg.
Intravenous administration of rabeprazole sodium in the rat at doses of 75 mg/kg for 14 days showed clinical signs such as hypoactivity, salivation, prone position, and flushing of the nose, but these signs disappeared after one hour of administration. Thymus weight was decreased and liver weight was increased.
Dog
Rabeprazole sodium had no effect on liver, kidney, heart, or lung at doses up to and including 30 mg/kg given by oral administration. Because of the smaller thymus weights observed in females treated with 30 mg/kg, the NOEL was 10 mg/kg.
Rabeprazole sodium (0.1, 0.3, or 1.0 mg/kg) and omeprazole (0.3, 1.0, or 3.0 mg/kg) were given orally to male and female dogs for 13 weeks followed by a 13-week recovery period. Expected pharmacologic responses (elevated gastrin levels and gastric changes) were observed with both proton pump inhibitors. Gastric changes were reversible at 0.3 mg/kg with both compounds and no gastric lesions were detected at 0.1 mg/kg of rabeprazole sodium. Effects were not observed in other organ systems with either compound.
In a one-year followed by a two-month reversibility phase study, soft and watery stools and emesis were among the observations made in dogs treated with 8 or 25 mg/kg rabeprazole sodium. Changes in clinical chemistry parameters included increases in cholesterol and triglycerides, and decreases in chloride and total protein. Serum gastrin levels, gross and histopathologic changes in stomach including increases in stomach weight, gastric mucosal and nonmucosal mass, and ECL hypertrophy and/or hyperplasia were observed in the rabeprazole-treated groups. The maximum tolerated dose was 8 mg/kg and the NOEL was 2 mg/kg.
In a 52-week study, a number of changes were observed in the stomach of dogs treated with 1 or 5 mg/kg of rabeprazole sodium. These changes included increased stomach weight, thickening of the gastric mucosa, chief cell cytoplasmic atrophy, foci of cellular and chromogranin positive cell hypertrophy, and elevated gastrin levels. These changes, considered to be the result of a prolonged pharmacological effect and not a toxic effect of rabeprazole sodium, were completely or partially reversed at the end of the recovery period.
In a 52-week study, over a dose range of 0.2 to 5 mg/kg, no change in ECL cell populations was evaluated.
In a 14-day study in the dog, rabeprazole was administered intravenously at doses of 1, 5, and 25 mg/kg. The lowest dose tested (1 mg/kg) was judged to be a no-effect-dose level for toxicity for rabeprazole in this study. At daily doses of 5 mg/kg, treatment-related findings included vomiting and stool changes and histopathologic changes in the thyroid and the stomach.
Pharmacologically Mediated Effects
In repeat-dose studies of up to one year in duration in rats and dogs and a three-month study in mice, trophic changes in the gastric mucosa were expected based on experience and the published literature of the H2-receptor antagonists and other proton pump inhibitors (Abe-1990, Ekman-1985, Hakanson-1986&1992, Atkinson-1990, Tuch-1992, Betton-1988, Creutzfeldt-1986, Poynter-1985&1991, Havu-1986&1990, Polak-1988). Gastric changes, stimulated by chronic and sustained acid suppression, were manifested by hypergastrinemia, ECL-cell hypertrophy, hyperplasia, and neoplasia (female rats only), chief cell eosinophilia, and fundic mucosal thickening in rats. Gastric changes were observed at low doses in these studies: 1 mg/kg-rat, 0.3 mg/kg-dog, 25 mg/kg-mouse. Increases in gastrin levels and trophic effects on the gastric mucosa were not observed at 0.2 mg/kg in a 52-week dog study. A four-week study in antrectromized rats treated with 40 mg/kg rabeprazole sodium revealed no increased levels of gastrin and no ECL cell hyperplasia indicating that chronic stimulation of G cells and gastrin release is critical in the pathogenesis of hypergastrinemia and trophic gastric lesions. Reversibility of non-neoplastic changes was demonstrated in several studies in rats, mice and dogs. In mice, diffuse neuroendocrine cell hyperplasia was fully restored and hyperplastic gastropathy was partially reversed after 13 or 26 weeks of recovery period.
Combination Studies with Rabeprazole, Amoxicillin and Clarithromycin
Single dose studies showed that the concomitant administration of the three drugs (rabeprazole, amoxicillin and clarithromycin) did not change the lethal dose or the onset of clinical signs when compared with administration of each drug alone. Mydriasis was attributed to the amoxicillin component.
Repeat dose studies showed that 25 mg/kg/day of rabeprazole given in combination with 1000 mg/kg/day of amoxicillin and 50 mg/kg/day of clarithromycin exceeded the maximum tolerated dose. Toxicological responses were not affected by combination treatment of rabeprazole/amoxicillin/clarithromycin at doses of 1/1000/50 or 5/1000/50 mg/kg/day.
Reproduction Studies
Because the oral bioavailability of rabeprazole sodium is low in rats and rabbits (less than 5%), rabeprazole was administered intravenously in the reproduction studies to maximize systemic exposure. Male and female fertility (+2 generations), embryo-fetal development (EFD) and perinatal/postnatal (+2 generations) studies, and effects on luteinizing hormone (LH) and testosterone (T) were completed.
In the fertility study (0, 1, 6, 30 mg/kg), no effects were observed on male or female fertility or on growth, development, or reproductive performance of the F1 generation. At maternally toxic doses (25 and 50 mg/kg) in the rat EFD study, incomplete ossification of the parietal and/or occipital bones was observed. There were no other effects on viability, weight or morphology. At maternally toxic doses (30 mg/kg) in the rabbit EFD study, decreased fetal weight and delayed ossification of the proximal tibial epiphysis was observed. There were no other effects on fetal viability or morphology. Adequate absorption of rabeprazole was demonstrated in the rabbit during the organogenesis period. In the perinatal/postnatal study in rats (0, 1, 6, 30 mg/kg), maternal toxicity was noted at 30 mg/kg, but this did not affect general reproductive performance or nursing of the dams. No effects on fetal development, parturition, lactation, postnatal growth and offspring development, or offspring reproductive performance were observed in this study.
Lansoprazole-induced Leydig cell tumours in the rat testes are related to an imbalance of LH regulation (Atkinson-1990). Rabeprazole does not cause Leydig cell tumours or perturbations of the LH/T axis.
Mutagenicity Studies
Rabeprazole was not genotoxic in the in vitro test for chromosome aberration in CHL/IU cells, the in vivo mouse micronucleus test, and the in vivo/ex vivo and in vitro unscheduled DNA synthesis assays in rat hepatocytes.
The CHO/HGPRT forward gene mutation assay: There was no evidence of induced mutation by treatment with rabeprazole at concentrations ranging from 10 to 40 μg/mL in the activated test. A weak response for mutagenicity was observed at concentrations ranging from 90 to 110 μg/mL in the absence of metabolic activation. However, this response was not reproducible. Treatment with either EMS or 3MC resulted in induction of HGPRT mutants. It was concluded that rabeprazole was not mutagenic in HGPRT+ Chinese hamster ovary cells.
Ames tests: Positive and negative results were observed. Positive results were seen with the carboxylic acid metabolite (M6) of rabeprazole which were attributable to contaminants originating from the reverse-phase chromatography column used for purifying M6.
The L5178Y TK mouse lymphoma assay: Rabeprazole was negative for inducing mutations in L5178Y TK+/- cells when testing in the absence of metabolic activation, but was weakly positive when tested at concentrations of 25 and 30 μg/mL in the presence of metabolic activation.
Carcinogenicity Studies
In a two-year carcinogenicity study in Fischer rats on a restricted feeding regime, ECL cell hyperplasia was observed but no gastric carcinoids were identified at doses up to 20 mg/kg/day (about 10 times the exposure on a body surface [mg/m2] basis for patients given the recommended 20 mg/day [12.3 mg/m2] dose).
A second two-year carcinogenicity study was conducted in Sprague-Dawley rats on an ad libitum feeding regime given oral doses of rabeprazole at 5, 15, 30 and 60 mg/kg/day for males and 5, 15, 30, 60 and 120 mg/kg/day for females (about 2-60 times the exposure on a body surface [mg/m2] basis for patients given the recommended 20 mg/day [12.3 mg/m2] dose). Although ECL cell hyperplasia was observed in both male and female rats and mice in the carcinogenicity studies, rabeprazole produced dose-related gastric carcinoids only in female Sprague-Dawley rats at doses ≥5 mg/kg. Rabeprazole was not observed to induce tumours in any other tissue.
In a two-year mouse carcinogenicity study, no drug-induced tumours were identified at doses up to 100 mg/kg/day (24 times exposure on a body surface [mg/m2] basis for patients given the recommended 20 mg/day [12.3 mg/m2] dose).
In a 28-week mouse carcinogenicity study, a group of male and female p53(+/-) C57BL/6 mice were administered rabeprazole daily by oral gavage at levels of 0 (vehicle control), 20, 60 or 200 mg/kg/day. A positive control group received a dose level of 400 mg/kg/day of p-cresidine daily by oral gavage in the same manner. Treatment-related non-neoplastic changes were described in the report as mucosal hyperplasia of the glandular stomach. These changes were attributable to pharmacologic effects of rabeprazole. There was no evidence of carcinogenic effect by rabeprazole treatment in the stomach. A small number of neoplasms (malignant lymphoma) were observed in the study. The incidence of malignant lymphoma was 1/20 in middose males; 1/20 in each of low-, mid- and high-dose group females (or 5%). Four female mice treated with rabeprazole died, three of them with malignant lymphoma. There was no dose response and the incidence of these neoplasms was not higher than expected based on the testing facility historical control data, or from data published by Storer, RD, et al. (that reported a historical incidence of malignant lymphoma in p53(+/-) C57BL/6 mice of 1.7-5.7% for males and 1.8-8% for females). The positive control group showed the expected tumour response, which is the development of mostly transitional cell carcinoma in the urinary bladder, thereby validating the study. The study was valid for detecting carcinogenic potential.
REFERENCES
- 1. Chiku S, Nakata H, Ishikawa T, Yuzuriha T. Pharmacokinetics of a new benzimidazole sulfoxide derivative, E3810 (1): Pharmacokinetics in rats and dogs. Yakubutsu Dotai (JSSX Journal) 1994; 9(5): 603-611.
- 2. Chiku S, Yoshimra T, Nakata H, Yuzuriha T. Pharmacokinetics of a new benzimidazole sulfoxide derivative, E3810 (2): Absorption, distribution, metabolism and excretion in rats. Yakubutsu Dotai (JSSX Journal) 1994; 9(5): 612-627.
- 3.
Danks A, Holmes P, Sparrow S, Virgo DM, Aloki T, Hayakawa K, et al. 52-week oral
(capsule) toxicity study with 26-week reversibility period in dogs with E3810. GI Research 1993;1(5):574-600.
- 4.
Fujusaki H, Shibata H, Okentani K, Murakami M, Fujimoto M, Wakabayashi T, et al.
Inhibitions of acid secretion by E3810 and omeprazole, and their reversal by glutathione. Biochem Pharmacol 1991; 42(2):321-8.
- 5. Ishizaki T, Chiba K, Manabe K, Koyama E, Hayashi M, Yasuda S, et al. Comparison of the interaction potential of a new proton pump inhibitor, E3810, versus omeprazole with diazepam in extensive and poor metabolizers of S-mephenytoin 4'-hydroxylation. Clin Pharmacol Ther 1995;58(2):155-64.
- 6.
Matsumoto N, Murakami Y, Komatsu H, Toge K, Yamazaki M, Kawamoto T, et al.
Effect of proton pump inhibitor, E3810 on intragastric pH. Proceedings of the Japanese Soc of Gastric Secretion Research 1991; 23:1-5.
- 7. Miner P Jr., Orr W, Filippone J, Jokubaitis L, Sloan S. Rabeprazole in nonerosive gastroesophageal reflux disease: A randomized placebo-controlled trial. Am J Gastroenterol 2002; 97(6):1332-1339.
- 8. Miyazaki Y, Imamura I, Yasunaga Y, Shinomura M, Fukui H, Wada H, et al. Effects of potent acid secretion inhibitors on gastrin secretion and histamine metabolism in the gastric mucosa. A study with the proton pump inhibitor E3810. Bulletin of Symposium of Gastric Secretion 1992; 24:93-6.
- 9.
Miwa H, Yamada T, Sato K, Ohta K, Ohkura R, Murai T, Nagahara A, Takei Y, Ogihara
T, Sata N. Efficacy of reduced dosage of rabeprazole in PPI/AC therapy for Helicobacter pylori infection: Comparison of 20 and 40 mg rabeprazole with 60 mg lansoprazole. Digestive Diseases and Sciences 2000; 45(1):77-82.
- 10. Miwa H, Ohkura R, Murai T, Sato K, Nagahara A, Hirai S, Watanabe S, Sato N. Impact of rabeprazole, a new proton pump inhibitor, in triple therapy for Helicobacter pylori infection. Comparison with omeprazole and lansoprazole. Alimentary Pharmacology & Therapeutics 1999; 13(6):741-746.
- 11. Morii M, Takata H, Fujisaki H, Takeguchi N. The potency of substituted benzimidazoles such as E3810, omeprazole, Ro 18-5364 to inhibit gastric H+, K+-ATPase is correlated with the rate of acid-activation of the inhibitor. Biochem Pharmacol 1990; 39:661-7.
- 12.
Morii M, Takeguchi N. Different biochemical modes of action of two irreversible H+,
K+-ATPase inhibitors, omeprazole and E3810. J Biol Chem 1993; 268(29):21553-9.
- 13. Noguchi M, Nakanowatari J, Tanabe Y, Tagaya O, Aoi T, Yamatsu K, et al. E3810 toxicity study in Beagle dogs after repeated oral administration for 13 weeks followed by a 5 week recovery period. GI Research 1993; 1(5 suppl.):527-56 (59-88).
- 14. Ohnishi A, Yasuda S, Ogawa T, Tomono Y, Hasegawa J, Morishita N. Results of phase I studies of E3810, a new proton pump inhibitor in healthy male volunteers. Single and multiple dose study. GI Research 1993;1(5):199-207.
- 15. Ohnishi A, Yasuda S, Ogawa T, Tomono Y, Hasegawa J, Morishita N. E3810 phase I clinical trial results - single and repeated administrations. GI Research 1993;1(5):667-75.
- 16. Okada F, Osumi I, Kawaguchi T, Yamatsu K, Igarashi T. Fetal organogenesis study in rabbits treated intravenously with E3810. GI Research 1993; 1 (5 suppl.): 647-54 (179-86).
- 17. Osumi I, Goto M, Okada F, Matsubara Y, Yamatsu K, Igarashi T. Fetal organogenesis study in rats treated orally with E3810. GI Research 1993; 1 (5 suppl.): 615-32 (147-64).
- 18. Shmizu M, Uto K, Kobayashi Y, Yamashita Y, Kato M, Shinoda A, et al. Perinatal and postnatal toxicity study of E3810 in rats after intravenous administration. GI Research 1993; 1 (5 suppl.): 633-46 (165-77).
- 19.
Stack WA, Knifton A, Thirlwell D, Cockayne A, Jenkins D, Hawkey CJ, Atherton
JC.Safety and efficacy of rabeprazole in combination with four antibiotic regimens for the eradication of Helicobacter pylori in patients with chronic gastritis with or without peptic ulceration. American Journal of Gastroenterology 1998; 93(10):1909-1913.
- 20. Storer RD, French JE, Haseman J, Jajian G, LeGrand EK, et al. p53+/- Hemizygous knockout mouse: Overview of available data. Toxicologic Pathology 2001; 29 (Suppl.): 30-50.
- 21. Verdu EF, Armstrong D, Fraser R et al. Effect of Helicobacter pylori status on intragastric pH during treatment with omeprazole. Gut 1995; 36:539-43.
- 22.
Williams MP, Sercombe J, Hamilton MI, Pounder RE. A placebo-controlled trial to assess the effects of 8 days of dosing with rabeprazole versus omeprazole on 24-h
intragastric acidity and plasma gastrin concentrations in young healthy male subjects. Aliment Pharmacol Ther 1998; 12:1079-1089.
- 23.
Wong BCY, Wong WM, Yee YK, Hung WK, Yip AWC, Szeto M, Li KF, Lau P, Fung
FMY, Tong TSM, Lai KC, Hu WHC, Yuen MF, Hui CK, Lam SK. Rabeprazole based 3-day and 7-day triple therapy versus 7-day omeprazole based triple therapy for the treatment of Helicobacter pylori infection. Alimentary Pharmacology Therapeutics 2001; 15: 1959-1965.
- 24. Yasuda S, Horai Y, Tomono Y, Nakai H, Yamato C, Manabe K, et al. Comparison of the kinetic disposition and metabolism of E3810, a new proton pump inhibitor, and omeprazole in relation to S-mephytoin 4-hydroxylation status. Clin Pharmacol Ther 1995; 58(2):143-54.
- 25.
Yasuda S, Ohnishi A, Ogawa T, Tomono Y, Hasegawa J, Nakai H, et al.
Pharmacokinetic properties of E3810, a new proton pump inhibitor, in healthy male volunteers. Int J ClinPharmacol Ther 1994; 32:466-73.
- 26. A double-blind, placebo-controlled trial of rabeprazole tablets, 20 mg once daily, in the treatment of subjects without erosive esophagitis and who have symptoms of chronic gastroesophageal reflux disease (GERD). Janssen Research Foundation, Data on File, 2001.
- 27.
Product Monograph for PARIET® (Janssen Inc. Canada) Control No. 161286 Date of
Revision: March 8, 2013.