


Product Monograph - AG-Pravastatin Tablets
Recent Major Label Changes
| 7 Warnings and Precautions, Musculoskeletal | 2026-06 |
|---|
Table of Contents
Certain sections or subsections that are not applicable at the time of the preparation of the most recent authorized product monograph are not listed.
Recent Major Label Changes .......................................................................................... 2
Table of Contents .......................................................................................................... 2
Part 1: Healthcare Professional Information .................................................................. 4
- 1.
Indications .............................................................................................................. 4
1.1 Pediatrics ....................................................................................................... 5
1.2 Geriatrics .............................................................................................................. 5
- 2. Contraindications ................................................................................................... 5
- 4.
Dosage and Administration .................................................................................... 6
4.1 Dosing Considerations ......................................................................................... 6
4.2 Recommended Dose and Dosage Adjustment .................................................... 6
4.5 Missed Dose ......................................................................................................... 7
- 5. Overdose ................................................................................................................ 7
- 6. Dosage Forms, Strengths, Composition, and Packaging .......................................... 8
- 7.
Warnings and Precautions ...................................................................................... 8
General ...................................................................................................................... 8
Carcinogenesis and Genotoxicity .............................................................................. 9
Endocrine and Metabolism ....................................................................................... 9
Hepatic/biliary/pancreatic ...................................................................................... 10
Immune .................................................................................................................... 11
Musculoskeletal ....................................................................................................... 11
Ophthalmologic ....................................................................................................... 13
Renal 13
Respiratory .............................................................................................................. 13
7.1 Special Populations ............................................................................................ 13
7.1.1 Pregnancy ....................................................................................................... 13
7.1.2 Breastfeeding .................................................................................................. 13
7.1.3 Pediatrics ........................................................................................................ 14
7.1.4 Geriatrics ......................................................................................................... 14
- 8.
Adverse Reactions ................................................................................................ 14
8.1 Adverse Reaction Overview .............................................................................. 14
8.2 Clinical Trial Adverse Reactions ......................................................................... 14
8.4 Abnormal Laboratory Findings: Hematologic, Clinical Chemistry, and Other Quantitative Data ........................................................................................ 18
8.5 Post-Market Adverse Reactions ........................................................................ 18
- 9.
Drug Interactions .................................................................................................. 20
9.4 Drug-Drug Interactions ...................................................................................... 20
9.5 Drug-Food Interactions ...................................................................................... 24
9.6 Drug-Herb Interactions ...................................................................................... 25
9.7 Drug-Laboratory Test Interactions .................................................................... 25
- 10.
Clinical Pharmacology .......................................................................................... 25
10.1 Mechanism of Action ....................................................................................... 25
10.2 Pharmacodynamics .......................................................................................... 26
10.3 Pharmacokinetics ............................................................................................ 27
- 11. Storage, Stability, and Disposal ............................................................................ 29
Part 2: Scientific Information ....................................................................................... 30
- 14.
Clinical Trials ........................................................................................................ 31
14.1 Clinical Trials by Indication .............................................................................. 31
14.2 Comparative Bioavailability Studies ................................................................ 36
SUMMARY TABLE OF THE COMPARATIVE BIOAVAILABILITY DATA ........................ 37
- 16. Non-Clinical Toxicology ........................................................................................ 37
General toxicology ....................................................................................................... 37
- 17. Supporting Product Monographs .......................................................................... 41
Patient Medication Information .................................................................................. 42
Part 1: Healthcare Professional Information
1. Indications
Therapy with lipid-altering agents should be considered a component of multiple risk factor intervention in those individuals at increased risk for atherosclerotic vascular disease due to dyslipidemia. AG-Pravastatin Tablets (pravastatin sodium) should be used in addition to a diet restricted in saturated fat and cholesterol when the response to diet and other non- pharmacological measures alone has been inadequate.
Hypercholesterolemia
- AG-Pravastatin Tablets is indicated as an adjunct to diet (at least an equivalent of the Adult Treatment Panel III [ATP III TLC diet]) for the reduction of elevated Total and Low Density Lipoprotein Cholesterol (LDL-C) levels in patients with primary hypercholesterolemia (Types IIa and IIb), when the response to diet and other non-pharmacologic measures alone has been inadequate.
- Prior to initiating therapy with AG-Pravastatin Tablets, secondary causes for hypercholesterolemia, such as obesity, poorly controlled diabetes mellitus, hypothyroidism, nephrotic syndrome, dysproteinemias, obstructive liver disease, other drug therapy or alcoholism, should be excluded and it should be determined that patients for whom treatment with AG-Pravastatin Tablets is being considered have an elevated LDL-C level as the cause for an elevated total serum cholesterol. A lipid profile should be performed to measure Total Cholesterol, High Density Lipoprotein Cholesterol (HDL-C) and Triglycerides (TG).
For patients with total triglycerides less than 4.52 mmol/L (400 mg/dL), LDL-C can be estimated using the following equation:
LDL-C (mmol/L) = Total Cholesterol - [(0.37 x triglycerides) + HDL-C]
LDL-C (mg/dL) = Total Cholesterol - [(0.16 x triglycerides) + HDL-C]
- When total triglyceride levels exceed 4.52 mmol/L (400 mg/dL), this equation is less accurate and LDL-C concentrations should be determined by ultracentrifugation.
- As with other lipid-lowering therapy, AG-Pravastatin Tablets is not indicated when hypercholesterolemia is due to hyperalphalipoproteinemia (elevated HDL-C). The efficacy of pravastatin has not been evaluated in conditions where the major abnormality is elevation of chylomicrons, VLDL or LDL (i.e. hyperlipoproteinemia or dyslipoproteinemia types I, III, IV or V).
Primary Prevention of Coronary Events
In hypercholesterolemic patients without clinically evident coronary heart disease, AG-Pravastatin Tablets is indicated to:
- Reduce the risk of myocardial infarction;
- Reduce the risk for undergoing myocardial revascularization procedures;
- Reduce the risk of total mortality by reducing cardiovascular deaths.
Secondary Prevention of Cardiovascular Events
In patients with total cholesterol in the normal to moderately elevated range who have clinically evident coronary heart disease, AG-Pravastatin Tablets is indicated to:
- Reduce the risk of total mortality
- Reduce the risk of death due to coronary heart disease
- Reduce the risk of myocardial infarction
- Reduce the risk of undergoing myocardial revascularization procedures
- Reduce the risk of stroke and transient ischemic attack (TIA)
- Reduce total hospitalization
Pravastatin was also found to reduce the rate of progression of atherosclerosis in patients with coronary heart disease as part of a treatment strategy to lower Total and LDL–cholesterol to desired levels. In two trials including this type of patients1 (i.e. in a secondary prevention intervention), pravastatin monotherapy was shown to reduce the rate of progression of atherosclerosis as evaluated by quantitative angiography and B-mode ultrasound. This effect may be associated with an improvement in the coronary endpoints (fatal or non-fatal myocardial infarction). In these trials, however, no effect was observed in all cause mortality (see 14.1 Clinical Trials by Indication, Atherosclerotic Disease Progression).
1.1 Pediatrics
Pediatrics (< 16 years of age): No data are available to Health Canada; therefore, Health Canada has not authorized an indication for pediatric use.
1.2 Geriatrics
Geriatrics (≥ 65 years of age): Pharmacokinetic evaluation of pravastatin in patients over the age of 65 years indicates an increased AUC. As a precautionary measure, the lowest dose should be administered initially in these patients.
2. Contraindications
AG-Pravastatin Tablets is contraindicated in:
- Patients who are hypersensitive to this drug or to any ingredient in the formulation, including any non-medicinal ingredient, or component of the container. For a complete listing, see 6 Dosage Forms, Strengths, Composition, and Packaging.
- Active liver disease or unexplained persistent elevations of serum transaminases exceeding 3 times the upper limit of normal (ULN). (see 7 Warnings and Precautions,
1.Pravastatin Limitation of Atherosclerosis in the Coronary/Carotid Arteries (PLAC I and II)
Hepatic/Biliary/Pancreatic).
In Pregnant and Nursing Women
Cholesterol and other products of cholesterol biosynthesis are essential components for fetal development (including synthesis of steroids and cell membranes). Since HMG-CoA reductase inhibitors such as AG-Pravastatin Tablets (pravastatin sodium) decrease cholesterol synthesis and possibly the synthesis of other biologically active substances derived from cholesterol, they may cause fetal harm when administered to pregnant women. AG-Pravastatin Tablets should be administered to women of childbearing age only when such patients are highly unlikely to conceive and have been informed of the possible harm. If the patient becomes pregnant while taking AG-Pravastatin Tablets, the drug should be discontinued immediately and the patient apprised of the potential harm to the fetus. Atherosclerosis being a chronic process, discontinuation of lipid metabolism regulating drugs during pregnancy should have little impact on the outcome of long-term therapy of primary hypercholesterolemia (see 7.1.1 Pregnancy and 7.1.2 Breastfeeding).
4. Dosage and Administration
4.1 Dosing Considerations
- Patients should be placed on a standard cholesterol-lowering diet (at least equivalent to the Adult Treatment Panel III [ATP III TLC diet]) before receiving AG-Pravastatin Tablets (pravastatin sodium), and should continue on this diet during treatment with AG-Pravastatin Tablets. If appropriate, a program of weight control and physical exercise should be implemented.
- Prior to initiating therapy with AG-Pravastatin Tablets, secondary causes for elevations in plasma lipid levels should be excluded. A lipid profile should also be performed.
4.2 Recommended Dose and Dosage Adjustment
Hypercholesterolemia and Coronary Heart Disease
- The recommended starting dose is 20 mg once daily at bed time. Patients who require a large dose reduction in LDL-C may be started at 40 mg once daily. The dose of 80 mg once daily should be reserved for patients who do not achieve their treatment goal with lower doses. AG-Pravastatin Tablets may be taken without regard to meals (see 10.1 Mechanism of Action).
- In patients with a history of significant renal or hepatic dysfunction, a starting dose of 10 mg daily is recommended.
Concomitant Therapy
Some patients may require combination therapy with one or more lipid- lowering agents.
- Pharmacokinetic interaction with pravastatin administered concurrently with nicotinic acid, or gemfibrozil did not statistically significantly affect the bioavailability of pravastatin. The combined use of pravastatin and fibrates should however generally be avoided (see 7 Warnings and Precautions, Musculoskeletal).
- The lipid-lowering effects of pravastatin sodium on Total and Low Density Lipoprotein Cholesterol are additive when combined with a bile acid- binding resin. However, when administering a bile acid-binding resin (e.g. cholestyramine, colestipol) and pravastatin, pravastatin sodium should not be administered concomitantly, but should be given either one hour or more before or at least four hours following the resin (see 9.4 Drug-Drug Interactions, Concomitant Therapy with Other Lipid Metabolism Regulators).
- In patients taking cyclosporine, with or without other immunosuppressive drugs, concomitantly with pravastatin, therapy should be initiated with 10 mg per day and titration to higher doses should be performed with caution. Most patients treated with this combination received a maximum pravastatin dose of 20 mg/day (see 9.4 Drug-Drug Interactions, Cyclosporine).
- The dosage of pravastatin sodium should be individualized according to baseline LDL-C, total- C/HDL-C ratio and/or TG levels to achieve the desired lipid values at the lowest possible dose.
4.5 Missed Dose
If you missed a dose of this medication, take it as soon as you remember. But if it is almost time for your next dose, skip the missed dose and continue with your next scheduled dose. Go back to the regular dosing schedule. Do not take two doses at the same time.
5. Overdose
There have been two reports of overdosage with pravastatin, both of which were asymptomatic and not associated with clinical laboratory abnormalities.
In the event of overdosage, treatment should be symptomatic and supportive, and appropriate therapy instituted. Until further experience is obtained, no specific therapy of overdosage can be recommended. The dialyzability of pravastatin and its metabolites is not known.
For the most recent information in the management of a suspected drug overdose, contact your regional poison control centre or Health Canada’s toll-free number, 1-844 POISON-X (1- 844-764-7669).
- 6. Dosage Forms, Strengths, Composition, and Packaging
Table 1 – Dosage Forms, Strengths, and Composition
| Route of Administration | Dosage Form/ Strength/Composition | Non-Medicinal Ingredients |
|---|---|---|
| Oral | Tablet 10 mg, 20 mg and 40 mg | Crospovidone, D&C yellow No. 10 aluminum lake (40 mg tablets only), FD&C blue No. 1 aluminum lake (40 mg tablets only), iron oxide red (10 mg tablets only), iron oxide yellow (20 mg tablets only), lactose anhydrous, magnesium oxide, magnesium stearate, microcrystalline cellulose and talc. |
Description
AG-Pravastatin Tablets 10 mg tablets: Each rounded rectangular shaped, pink to peach, biconvex, tablet with “P10” debossed on one side and “JP” on the other, contains
10 mg of pravastatin sodium. Available in bottles of 100 tablets and in unit dose Alu-Alu blisters of 30 tablets.
AG-Pravastatin Tablets 20 mg tablets: Each rounded rectangular shaped, yellow, biconvex, tablet with “P20” debossed on one side and “JP” on the other, contains 20 mg of pravastatin sodium. Available in bottles of 100 tablets and in unit dose Alu-Alu blisters of 30 tablets.
AG-Pravastatin Tablets 40 mg tablets: Each rounded rectangular shaped, green, biconvex, tablet with “P40” debossed on one side and “JP” on the other, contains 40 mg of pravastatin sodium. Available in bottles of 100 tablets and in unit dose Alu-Alu blisters of 30 tablets.
7. Warnings and Precautions
General
Before instituting therapy with pravastatin sodium, an attempt should be made to control hypercholesterolemia with appropriate diet, exercise, weight reduction in overweight and obese patients, and to treat other underlying medical problems (see 1 Indications). The patient should be advised to inform subsequent physicians of the prior use of pravastatin sodium.
Pravastatin may elevate creatine phosphokinase and transaminase levels. This should be considered in the differential diagnosis of chest pain in a patient on therapy with pravastatin.
Homozygous Familial Hypercholesterolemia: Pravastatin has not been evaluated in patients with rare homozygous familial hypercholesterolemia. Most HMG-CoA reductase inhibitors are less or not effective in this subgroup of hypercholesterolemic patients.
Effect on Lipoprotein (a): In some patients, the beneficial effect of lowered total cholesterol and LDL-C levels may be partly blunted by a concomitant increase in the Lipoprotein (a) [Lp (a)] level. Further research is ongoing to elucidate the significance of Lp (a) variations. Therefore, until further experience is obtained, where feasible, it is suggested that measurements of serum Lp (a) be followed up in patients placed on pravastatin therapy.
Effect on CoQ10 Levels (Ubiquinone): A significant short-term decrease in plasma CoQ10 levels in patients treated with pravastatin sodium has been observed. Longer clinical trials have also shown reduced serum ubiquinone levels during treatment with pravastatin and other HMG CoA reductase inhibitors. The clinical significance of a potential long-term statin-induced deficiency of CoQ10 has not yet been established. It has been reported that a decrease in myocardial ubiquinone levels could lead to impaired cardiac function in patients with borderline congestive heart failure.
Carcinogenesis and Genotoxicity
A 21-month oral study in mice, with doses of 10 to 100 mg/kg daily of pravastatin did not demonstrate any carcinogenic potential. In a 2-year oral study in rats, a statistically significant increase in the incidence of hepatocellular carcinoma was observed in male rats given 100 mg/kg daily (60 times the maximum human dose) of pravastatin. This change was not seen in male rats given 40 mg/kg daily (25 times the recommended human dose) or less, or in female rats at any dose level.
Endocrine and Metabolism
HMG-CoA reductase inhibitors interfere with cholesterol synthesis and as such could theoretically blunt adrenal and/or gonadal steroid production.
In one long-term study investigating the endocrine function in hypercholesterolemic patients, pravastatin sodium exhibited no effect upon basal and stimulated cortisol levels, as well as on aldosterone secretion. Although no change was reported in the testicular function, conflicting results were observed in the analysis of sperm motility after administration of pravastatin sodium. A case of reversible impotence has been reported in a 57-year old man administered pravastatin 20 mg/day and metoprolol. A causal relationship to therapy with pravastatin sodium has not been established. Further studies are needed to clarify the effects of HMG CoA reductase inhibitors on male fertility. Furthermore, the effects, if any, on the pituitary-gonadal axis in premenopausal women are unknown.
Patients treated with pravastatin sodium who develop clinical evidence of endocrine dysfunction should be evaluated appropriately. Caution should be exercised if an HMG-CoA reductase inhibitor or other agent used to lower cholesterol levels is administered to patients receiving other drugs (e.g. ketoconazole, spironolactone, or cimetidine) that may decrease the levels of endogenous steroid hormones.
Increases in fasting glucose and HbA1c levels have been reported with inhibitors of HMG-CoA reductase as a class. For some patients at high risk of diabetes mellitus, hyperglycemia was sufficient to shift them to diabetes status. The benefit of treatment continues to outweigh the small increased risk. Periodic monitoring of these patients is recommended.
Patients with Severe Hypercholesterolemia: Higher doses (≥40 mg/day) required for some patients with severe hypercholesterolemia are associated with increased plasma levels of pravastatin. Caution should be exercised in such patients who are also significantly renally impaired or elderly (see 7 Warnings and Precautions, Musculoskeletal).
Hepatic/biliary/pancreatic
HMG-CoA reductase inhibitors have been associated with biochemical abnormalities of liver function. As with other lipid-lowering agents, including non-absorbable bile acid-binding resins, increases in liver enzymes to less than three times the upper limit of normal have occurred during therapy with pravastatin. The significance of these changes, which usually appear during the first few months of treatment initiation, is not known. In the majority of patients treated with pravastatin, in clinical trials, these increased values declined to pretreatment levels despite continuation of therapy at the same dose.
Marked persistent increases (greater than three times the upper limit of normal) in serum transaminases were seen in 6 out of 1142 (0.5%) patients treated with pravastatin in clinical trials (see 8 Adverse Reactions). The increases usually appeared 3 to 12 months after the start of therapy with pravastatin sodium. These elevations were not associated with clinical signs and symptoms of liver disease and usually declined to pretreatment levels upon discontinuation of therapy. Patients rarely had persistent marked abnormalities possibly attributable to therapy. In the largest long-term placebo-controlled trial with pravastatin (Pravastatin Primary Prevention Study/ WOSCOPS), no patient with normal liver function after 12 weeks of treatment (N=2875 pravastatin-treated patients) had subsequent ALT elevations greater than three times the upper limit of normal on two consecutive measurements. Two of these 2875 patients treated with pravastatin (0.07%) and one of 2919 placebo patients (0.03%) had elevations of AST greater than three times the upper limit of normal on two consecutive measurements during the 4.8 years (median treatment) of the study.
Liver function tests should be performed at baseline and at 12 weeks following initiation of therapy or the elevation of dose. Special attention should be given to patients who develop increased transaminase levels. Liver function tests should be repeated to confirm an elevation and subsequently monitored at more frequent intervals. If increases in alanine aminotransferase (ALAT) and aspartate aminotransferase (ASAT) equal or exceed three times the upper limit of normal and persist, therapy should be discontinued.
There have been rare post-marketing reports of fatal and non-fatal hepatic failure in patients taking statins, including pravastatin sodium. If serious liver injury with clinical symptoms and/or hyperbilirubinemia or jaundice occurs during treatment with pravastatin sodium, promptly interrupt therapy. If an alternate etiology is not found, do not restart pravastatin sodium.
Pravastatin sodium, as well as other HMG-CoA reductase inhibitors should be used with caution in patients who consume substantial quantities of alcohol and/or have a past history of liver disease. Active liver disease or unexplained serum transaminase elevations are contraindications to the use of pravastatin sodium; if such condition develops during therapy, the drug should be discontinued.
Immune
Hypersensitivity: With lovastatin an apparent hypersensitivity syndrome has been reported rarely which has included one or more of the following features: anaphylaxis, angioedema, lupus-like syndrome, polymyalgia rheumatica, thrombocytopenia, leukopenia, hemolytic anemia, positive antinuclear antibody (ANA), erythrocytes sedimentation rate (ESR) increase, arthritis, arthralgia, urticaria, asthenia, photosensitivity, fever and malaise.
Although to date hypersensitivity syndrome has not been described as such, in few instances eosinophilia and skin eruptions appear to be associated with pravastatin sodium treatment. If hypersensitivity is suspected AG-Pravastatin Tablets should be discontinued. Patients should be advised to report promptly any signs of hypersensitivity such as angioedema, urticaria, photosensitivity, polyarthralgia, fever, malaise.
Immune-Mediated Necrotizing Myopathy (IMNM): There have been rare reports of immune- mediated necrotizing myopathy (IMNM), an autoimmune myopathy associated with statin use. IMNM is characterized by:
- proximal muscle weakness and elevated creatine kinase, which persist despite discontinuation of statin treatment
- muscle biopsy showing necrotizing myopathy without significant inflammation
- improvement with immunosuppressive agents.
Musculoskeletal
Elevations of creatinine phosphokinase levels (CK [MM fraction]), have been reported with the use of HMG-CoA reductase inhibitors, including pravastatin sodium.
Effects on skeletal muscle such as myalgia, myopathy and, rarely, rhabdomyolysis have been reported in patients treated with pravastatin sodium.
Muscle weakness and rhabdomyolysis have been reported in patients receiving other HMG-CoA reductase inhibitors concomitantly with itraconozole and cyclosporine.
The benefits and risks of using HMG-CoA reductase inhibitors concomitantly with immunosuppressive drugs, fibrates, erythromycin, systemic azole derivative antifungal agents or lipid-lowering doses of niacin should be carefully considered.
Rare cases of rhabdomyolysis with acute renal failure secondary to myoglobinuria have been reported with pravastatin sodium and with other HMG-CoA reductase inhibitors.
Muscle strains and tears, including muscle rupture, have been reported with pravastatin sodium.
Myopathy, defined as muscle pain or muscle weakness in conjunction with increases in creatine phosphokinase (CK) values to greater than ten times the upper limit of normal, should be considered in any patient with diffuse myalgias, muscle tenderness or weakness, and/or marked elevation of CK. Patients should be advised to report promptly any unexplained muscle pain, tenderness or weakness, particularly if associated with malaise or fever. Patients who develop any signs or symptoms suggestive of myopathy should have their CK levels measured. AG-Pravastatin Tablets should be discontinued if markedly elevated CK levels are measured or myopathy is diagnosed or suspected.
As with other statins, the risk of myopathy including rhabdomyolysis may be substantially increased by concomitant immunosuppressive therapy including cyclosporines, and by concomitant therapy with gemfibrozil, erythromycin or niacin.
Myopathy has not been observed in clinical trials involving small numbers of patients who were treated with pravastatin sodium together with immunosupressants, fibric acid derivatives or niacin (see 14 Clinical Trials).
The use of fibrates alone is occasionally associated with myopathy. In a limited size clinical trial of combined therapy with pravastatin (40 mg/day) and gemfibrozil (1200 mg/day), myopathy was not reported, although a trend towards CK elevations and musculoskeletal symptoms was seen. The combined use of pravastatin and fibrates should generally be avoided.
No information is available on the combined therapy of pravastatin with erythromycin.
Pre-disposing Factors for Myopathy/Rhabdomyolysis: Pravastatin sodium, as with other HMG- CoA reductase inhibitors, should be prescribed with caution in patients with pre-disposing factors for myopathy/rhabdomyolysis. Such factors include:
- Personal or family history of hereditary muscular disorders
- Previous history of muscle toxicity with another HMG-CoA reductase inhibitor
- Concomitant use of a fibrate or niacin
- Uncontrolled hypothyroidism
- Alcohol abuse
- Excessive physical exercise
- Advance age > 65 years
- Renal impairment
- Hepatic impairment
- Diabetes with hepatic fatty change
- Surgery and trauma
- Frailty
- Situation where an increase in plasma levels of active ingredient may occur.
AG-Pravastatin Tablets should be temporarily withheld or discontinued in any patient with an acute serious condition suggestive of myopathy or predisposing to the development of rhabdomyolysis (e.g. sepsis, hypotension, major surgery, trauma, severe metabolic endocrine and electrolyte disorders, or uncontrolled seizures).
Myasthenia Gravis/Ocular Myasthenia: Statins may in rare instances induce or aggravate the conditions in patients with myasthenia gravis or ocular myasthenia (see 8.5 Post-Market Adverse Reactions) including causing recurrence when the same or a different statin was administered. AG-Pravastatin Tablets should be used with caution in patients with these conditions and should be discontinued if the symptoms are induced or aggravated.
Ophthalmologic
Effect on the Lens: Current data from clinical trials do not indicate an adverse effect of pravastatin on the human lens.
Renal
There have been no studies on the use of pravastatin in patients with renal insufficiency. As a precautionary measure, the lowest dose should be used in these patients (see 7 Warnings and Precautions, Musculoskeletal).
Respiratory
Interstitial lung disease: Exceptional cases of interstitial lung disease have been reported with some statins, including pravastatin, especially with long term therapy (see 8.5 Post-Market Adverse Reactions). Presenting features can include dyspnoea, non-productive cough and deterioration in general health (fatigue, weight loss, and fever). If it is suspected a patient has developed interstitial lung disease, statin therapy should be discontinued.
7.1 Special Populations
7.1.1 Pregnancy
AG-Pravastatin Tablets is contraindicated during pregnancy (see 2 Contraindications).
Safety in pregnant women has not been established. Although pravastatin was not teratogenic in rats at doses as high as 1000 mg/kg daily nor in rabbits at doses of up to 50 mg/kg daily, AG-Pravastatin Tablets should be administered to women of childbearing age only when such patients are highly unlikely to conceive and have been informed of potential hazards. If a woman becomes pregnant while taking AG-Pravastatin Tablets, AG-Pravastatin Tablets should be discontinued and the patient advised again as to the potential hazards to the fetus.
7.1.2 Breastfeeding
A negligible amount of pravastatin is excreted in human breast milk. Because of the potential for adverse reactions in nursing infants, if the mother is being treated with AG-Pravastatin Tablets, nursing should be discontinued or treatment with AG-Pravastatin Tablets stopped.
7.1.3 Pediatrics
Pediatrics (<16 years of age): Only limited experience with the use of statins in children is available (see 17 Supporting Product Monographs). There is no experience to date with the use of pravastatin sodium in such patients. Treatment in these patients is not recommended at this time.
7.1.4 Geriatrics
Geriatrics (≥65 years of age): Pharmacokinetic evaluation of pravastatin in patients over the age of 65 years indicates an increased AUC. There were no reported increases in the incidence of adverse effects in these or other studies involving patients in that age group. As a precautionary measure, the lowest dose should be administered initially.
Elderly patients may be more susceptible to myopathy (see 7 Warnings and Precautions, Musculoskeletal, Pre-disposing Factors for Myopathy/Rhabdomyolysis).
8. Adverse Reactions
8.1 Adverse Reaction Overview
Pravastatin is generally well tolerated. Adverse events have been usually mild to moderate and transient. Adverse events observed or reported in short-and long-term trials are as follows.
8.2 Clinical Trial Adverse Reactions
Clinical trials are conducted under very specific conditions. Therefore the frequencies of adverse reactions observed in the clinical trials may not reflect frequencies observed in clinical practice and should not be compared to frequencies reported in clinical trials of another drug.
Short-term Controlled Trials
All adverse clinical events (regardless of attribution) reported in more than 2% of pravastatin- treated patients in placebo-controlled trials of up to four months duration are identified in the following table; also shown are the percentages of patients in whom these medical events were believed to be related or possibly related to the drug.
Table 2 - Adverse Events in > 2 Percent of Patients Treated with Pravastatin 10 to 40 mg in Short-Term Placebo-Controlled Trials
| System organ class/preferred term | All Events | Events Attributed to Study Drug | ||||||||
|---|---|---|---|---|---|---|---|---|---|---|
| System organ class/preferred term | All Events | Events Attributed to Study Drug | ||||||||
Pravastatin (N=900) % of patients | Placebo (N=411) % of patients | Pravastatin (N=900) % of patients | Placebo (N=411) % of patients | |||||||
Pravastatin (N=900) % of patients | Placebo (N=411) % of patients | Pravastatin (N=900) % of patients | Placebo (N=411) % of patients | |||||||
| Cardiac disorders | ||||||||||
| Cardiac Chest Pain | 4.0 | 3.4 | 0.1 | 0.0 | ||||||
| Gastrointestinal disorders | ||||||||||
| Nausea/Vomiting | 7.3 | 7.1 | 2.9 | 3.4 | ||||||
| Diarrhea | 6.2 | 5.6 | 2.0 | 1.9 | ||||||
| Abdominal Pain | 5.4 | 6.9 | 2.0 | 3.9 | ||||||
| Constipation | 4.0 | 7.1 | 2.4 | 5.1 | ||||||
| Flatulence | 3.3 | 3.6 | 2.7 | 3.4 | ||||||
| Heartburn | 2.9 | 1.9 | 2.0 | 0.7 | ||||||
| General disorders and administration site conditions | ||||||||||
| Fatigue | 3.8 | 3.4 | 1.9 | 1.0 | ||||||
| Chest Pain | 3.7 | 1.9 | 0.3 | 0.2 | ||||||
| Influenza | 2.4* | 0.7 | 0.0 | 0.0 | ||||||
| Musculoskeletal and connective tissue disorders | ||||||||||
| Localized Pain | 10.0 | 9.0 | 1.4 | 1.5 | ||||||
| Myalgia | 2.7 | 1.0 | 0.6 | 0.0 | ||||||
| Nervous system disorders | ||||||||||
| Headache | 6.2 | 3.9 | 1.7* | 0.2 | ||||||
| Dizziness | 3.3 | 3.2 | 1.0 | 0.5 | ||||||
| Renal and urinary disorders | ||||||||||
| Urinary Abnormality | 2.4 | 2.9 | 0.7 | 1.2 | ||||||
| Respiratory, thoracic and mediastinal disorders | ||||||||||
| Common Cold | 7.0 | 6.3 | 0.0 | 0.0 | ||||||
| Rhinitis | 4.0 | 4.1 | 0.1 | 0.0 | ||||||
| Cough | 2.6 | 1.7 | 0.1 | 0.0 | ||||||
| Skin and subcutaneous tissue disorders | ||||||||||
| Rash | 4.0 | 1.1 | 1.3 | 0.9 | ||||||
* Statistically significantly different from placebo
The safety and tolerability of pravastatin sodium at a dose of 80 mg in two controlled trials with a mean exposure of 8.6 months was similar to that of pravastatin sodium at lower doses except that 4 out of 464 patients taking 80 mg of pravastatin had a single elevation of CK > 10X ULN compared to 0 out of 115 patients taking 40 mg of pravastatin.
Long-Term Controlled Morbidity and Mortality Trials
In seven randomized, double-blind, placebo-controlled trials involving over 21,500 patients treated with pravastatin (N=10,784) or placebo (N=10,719), the safety and tolerability in the pravastatin group was comparable to that of the placebo group. Over 19,000 patients were followed for a median of 4.8 to 5.9 years, while the remaining patients were followed for two years or more.
Clinical adverse events probably or possibly related, or of uncertain relationship to therapy, occurring in at least 0.5% of patients treated with pravastatin or placebo in these long-term morbidity/mortality trials are shown in the table below:
Table 3 - Adverse Events occurring in at least 0.5% of Patients treated with Pravastatin or placebo in Long-Term morbidity/mortality Trials
| System organ class/preferred term | Pravastatin (N=10,784) % | Placebo (N=10,719) % |
|---|---|---|
| System organ class/preferred term | Pravastatin (N=10,784) % | Placebo (N=10,719) % |
| System organ class/preferred term | Pravastatin (N=10,784) % | Placebo (N=10,719) % |
| Cardiac disorders | ||
| Angina pectoris | 3.1 | 3.4 |
| Disturbance rhythm subjective | 0.8 | 0.7 |
| Hypertension | 0.7 | 0.9 |
| Edema | 0.6 | 0.6 |
| Myocardial infarction | 0.5 | 0.7 |
| Ear and labyrinth disorders | ||
| Hearing abnormality (includes tinnitus and hearing loss) | 0.6 | 0.5 |
| Eye Disorders | ||
| Vision disturbance (includes blurred vision) | 1.5 | 1.3 |
| Disturbance eye (includes eye inflammation) | 0.8 | 0.9 |
| Lens opacity | 0.5 | 0.4 |
| Gastrointestinal disorders | ||
| Dyspepsia / heartburn | 3.5 | 3.7 |
| Nausea / vomiting | 1.4 | 1.6 |
| Flatulence | 1.2 | 1.1 |
| Constipation | 1.2 | 1.3 |
| Diarrhea | 0.9 | 1.1 |
| Abdominal pain | 0.9 | 1.0 |
| Distention abdomen | 0.5 | 0.5 |
| General disorders and administration site conditions | ||
| Fatigue | 3.4 | 3.3 |
| Chest pain | 2.6 | 2.6 |
| Weight gain | 0.6 | 0.7 |
| Influenza | 0.6 | 0.5 |
| Musculoskeletal and connective tissue disorders | ||
| Musculoskeletal Pain (includes arthralgia) | 5.9 | 5.7 |
| Muscle cramp | 2.0 | 1.8 |
| Myalgia | 1.4 | 1.4 |
| Musculoskeletal trauma | 0.5 | 0.3 |
| Nervous System disorders | ||
| Dizziness | 2.2 | 2.1 |
| Headache | 1.9 | 1.8 |
| Sleep disturbance | 1.0 | 0.9 |
| Depression | 1.0 | 1.0 |
| Anxiety / nervousness | 1.0 | 1.2 |
| Paresthesia | 0.9 | 0.9 |
| Numbness | 0.5 | 0.4 |
| Renal and urinary disorders | ||
| Urinary abnormality (includes dysuria and nocturia) | 1 | 0.8 |
| Respiratory, thoracic and mediastinal disorders | ||
| Dyspnea | 1.6 | 1.6 |
| Upper respiratory infection | 1.3 | 1.3 |
| Cough | 1.0 | 1.0 |
| Sinus abnormality (includes sinusitis) | 0.8 | 0.8 |
| Pharyngitis | 0.5 | 0.6 |
| Skin and subcutaneous tissue disorders | ||
| Rash | 2.1 | 2.2 |
| Pruritus | 0.9 | 1.0 |
8.4 Abnormal Laboratory Findings: Hematologic, Clinical Chemistry, and Other Quantitative Data
Increases in serum transaminases and in creatine phosphokinase (CK) in patients treated with pravastatin sodium have been discussed (see 7 Warnings and Precautions, Musculoskeletal).
8.5 Post-Market Adverse Reactions
The following adverse events have also been rarely reported during post-marketing experience with pravastatin sodium, regardless of causality assessment:
Blood and Lymphatic system disorders: hemolytic anemia, thrombocytopenia.
Cardiac Disorders: angioedema.
Ear and Labyrinth disorders: tinnitus
Endocrine disorders: increase in fasting glucose and HbA1C.
Eye disorders: eye symptoms (including soreness, dryness or itching), ocular myasthenia.
Gastrointestinal disorders: taste disturbance, pancreatitis, abnormal stool and appetite change.
General disorders and administration site conditions: chest pain (non cardiovascular), weakness, excess sweating hot flashes and fever, asthenia, chills, malaise.
Hepatobiliary disorders: hepatitis and fulminant hepatic necrosis, fatal and non-fatal hepatic failure, jaundice (including cholestatic), fatty change in liver, cirrhosis, hepatoma, abnormal stool and appetite change. Liver Function Test (LFT) abnormalities have also been reported.
Immune system disorders: anaphylaxis, lupus erythematosus-like syndrome, rheumatica, dermatomyositis, vasculitis, positive ANA, toxic epidermal necrolysis, erythema multiforme, including Stevens-Johnson syndrome, allergy.
Investigations: ESR increase.
Musculoskeletal and connective tissue disorders: myopathy, rhabdomyolysis, muscle strains, tears and rupture, tendon disorder (specifically tendonitis and tendon rupture), polymyositis and immune mediated necrotizing myopathy, polymyalgia, arthritis, arthralgia, myasthenia gravis.
Nervous System disorders: dysfunction of certain cranial nerves (including alteration of taste, impairment of extra-ocular movement, facial paresis), peripheral nerve palsy, paresthesia equilibrium disturbance, vertigo, memory impairment, tremor, mood change, mood related disorders including depression, sleep disturbances including insomnia and nightmares.
Reproductive system and breast disorders: gynecomastia, impotence (see 7 Warnings and Precautions, Endocrine and Metabolism), urticaria, sexual dysfunction, libido change.
Respiratory, Thoracic and mediastinal disorders: Very rare cases of interstitial lung disease, especially with long term therapy. If it is suspected a patient has developed interstitial lung disease, statin therapy should be discontinued.
Skin and subcutaneous tissue disorders: a variety of skin changes (pruritis, scalp hair abnormalities, skin dryness and dermatitis), purpura, photosensitivity reaction.
There have been rare post-marketing reports of cognitive impairment (e.g., memory loss, forgetfulness, amnesia, memory impairment, confusion) associated with statin use. These cognitive issues have been reported for all statins. The reports are generally non-serious and reversible upon statin discontinuation, with variable times to symptom onset (1 day to years) and symptom resolution (median of 3 weeks).
The following have also been reported with other statins: hepatitis, cholestatic jaundice, anorexia, psychic disturbances including anxiety, hypospermia, hypersensitivity, and increase in fasting glucose and HbA1C (see 7 Warnings and Precautions, Endocrine and Metabolism).
Lens
Current data from clinical trials do not indicate an adverse effect of pravastatin on the human lens.
9. Drug Interactions
9.4 Drug-Drug Interactions
The drugs listed in this table are based on either drug interaction case reports or studies, or potential interactions due to the expected magnitude and seriousness of the interaction (i.e., those identified as contraindicated).
Table 4 – Established or Potential Drug-Drug Interactions
| Non-proprietary name(s) of the drug product(s) | Source of evidence | Effect | Clinical comment |
|---|---|---|---|
| Non-proprietary name(s) of the drug product(s) | Source of evidence | Effect | Clinical comment |
| Non-proprietary name(s) of the drug product(s) | Source of evidence | Effect | Clinical comment |
| Non-proprietary name(s) of the drug product(s) | Source of evidence | Effect | Clinical comment |
| Antacids and Cimetidine | T | On the average, antacids (one hour prior to pravastatin sodium) reduce and cimetidine increases the bioavailability of pravastatin. These changes were not statistically significant. The clinical significance of these interactions is not known but is probably minimal as judged from the interaction with food (see 10.2 Pharmacodynamics). | |
| Antipyrine | T | Antipyrine was used as a model for drugs metabolized by the microsomal hepatic enzyme system (cytochrome P450 system). Pravastatin had no effect on the pharmacokinetics of antipyrine. | |
| Bile Acid Sequestrants | T | Preliminary evidence suggests that the cholesterol-lowering effects of pravastatin sodium and the bile acid sequestrants, cholestyramine/colestipol are additive. Concomitant administration resulted in an approximately 40 to 50% decrease in the mean AUC of pravastatin (see 4.2 Recommended Dose and Dosage Adjustment). | When pravastatin was administered one hour before or four hours after cholestyramine or one hour before colestipol and a standard meal, there was no clinically significant decrease in bioavailability or therapeutic effect. |
| Concomitant Therapy with Other Lipid Metabolism Regulators | CT | Based on post-marketing surveillance, gemfibrozil, fenofibrate, other fibrates and lipid lowering doses of niacin (nicotinic acid) may increase the risk of myopathy when given concomitantly with HMG- CoA reductase inhibitors, probably because they can produce myopathy when given alone (see 7 Warnings and Precautions, Musculoskeletal). | Combined drug therapy should be approached with caution. |
| Coumarin Anticoagulants | T | Pravastatin had no clinically significant effect on prothrombin time when administered in a study to normal elderly subjects who were stabilized on warfarin. | |
| Cyclosporine | CT | Several studies show that cyclosporine appears to increase pravastatin plasma concentration by several folds. In a multicentre study, the AUC values of pravastatin were shown to be five- fold higher in the presence of cyclosporine. There was no accumulation of pravastatin after multiple doses (see 4 Dosage and Administration and 17 Supporting Product Monographs). | |
| Digoxin | T | Coadministration of digoxin and other HMG CoA reductase inhibitors has been shown to increase the | As a precautionary measure, patients taking digoxin should be closely monitored. |
| steady state digoxin concentrations. The potential effects of coadministration of digoxin and pravastatin sodium are not known. | |||
| Diuretics, antihypertensives, angiotensin converting- enzyme (ACE) inhibitors, calcium channel blockers, or nitroglycerin. | T | Although specific interaction studies were not performed during clinical trials, no noticeable drug interactions were reported when pravastatin sodium was added to diuretics, antihypertensives, angiotensin converting- enzyme (ACE) inhibitors, calcium channel blockers, or nitroglycerin. | |
| Erythromycin | T | No information is available regarding interactions with erythromycin (see 7 Warnings and Precautions, Musculoskeletal). | |
| Gemfibrozil and nicotinic acid | CT | Gemfibrozil and nicotinic acid do not statistically significantly affect the bioavailability of pravastatin. However, in a limited size clinical trial, a trend toward CK elevations and musculoskeletal symptoms was seen in patients treated concurrently with pravastatin and gemfibrozil. Myopathy, including rhabdomyolysis, has occurred in patients who were receiving co- administration of HMG- CoA | |
| reductase inhibitors with fibric acid derivatives and niacin, particularly in subjects with pre-existing renal insufficiency (see7 Warnings and Precautions, Musculoskeletal). | |||
| Macrolides | T | Macrolides have the potential to increase statin exposure while used in combination. | Pravastatin should be used cautiously with macrolide antibiotics due to potential increased risk of myopathies. |
| Propranolol | T | Co-administration of propranolol and pravastatin reduced the AUC values by 23% and 16% respectively. | |
| Other Concomitant Therapy | CT | The use of HMG CoA reductase inhibitors has been associated with severe myopathy, including rhabdomyolysis, which may be more frequent when they are administered with drugs that inhibit the cytochrome P-450 enzyme system. In vitro and in vivo data indicate that pravastatin is not metabolized by cytochrome P450 3A4 to a clinically significant extent. This has been shown in studies with known cytochrome P450 3A4 inhibitors. | |
Legend: C = Case Study; CT = Clinical Trial; T = Theoretical
9.5 Drug-Food Interactions
Interactions with food have not been established.
9.6 Drug-Herb Interactions
Interactions with herbal products have not been established.
9.7 Drug-Laboratory Test Interactions
Pravastatin may elevate creatine phosphokinase and transaminase levels. This should be considered in the differential diagnosis of chest pain in a patient on therapy with pravastatin.
10. Clinical Pharmacology
10.1 Mechanism of Action
Pravastatin sodium is one of a new class of lipid-lowering compounds known as HMG-CoA reductase inhibitors (statins) that reduce cholesterol biosynthesis. These agents are competitive inhibitors of 3-hydroxy-3-methylglutaryl-coenzyme A (HMG-CoA) reductase, the enzyme catalyzing the early rate-limiting step in cholesterol biosynthesis, conversion of HMG- CoA to mevalonate. Pravastatin is isolated from a strain of Penicillium citrinum. The active drug substance is the hydroxyacid form.
Pravastatin sodium produces its lipid-lowering effect in two ways. First, as a consequence of its reversible inhibition of HMG-CoA reductase activity, it effects modest reductions in intracellular pools of cholesterol. This results in an increase in the number of Low Density Lipoproteins (LDL)
- receptors on cell surfaces and enhanced receptor-mediated catabolism and clearance of circulating LDL. Second, pravastatin inhibits LDL production by inhibiting hepatic synthesis of Very Low Density Lipoproteins (VLDL), the LDL precursor.
Epidemiologic and clinical investigations have associated the risk of coronary artery disease (CAD) with elevated levels of Total–C, LDL–C and decreased levels of HDL–C. These abnormalities of lipoprotein metabolism are considered as major contributors to the development of the disease. Other factors, e.g. interactions between lipids/ lipoproteins and endothelium, platelets and macrophages, have also been incriminated in the development of human atherosclerosis and of its complications.
In long-term prospective clinical trials effective treatment of hypercholesterolemia/dyslipidemia has consistently been associated with a reduction in the risk of CAD.
Treatment with pravastatin sodium has been shown to reduce circulating Total-C, LDL-C, and apolipoprotein B, modestly reduce VLDL-C and triglycerides (TG) while producing increases of variable magnitude in HDL-C and apolipoprotein A. Clinical trials suggest that pravastatin’s effect on reducing clinical events appears to incorporate both cholesterol modification and some ancillary mechanism.
Pravastatin has complex pharmacokinetic characteristics.
10.2 Pharmacodynamics
In both normal volunteers and patients with hypercholesterolemia, treatment with pravastatin sodium reduced total-C, LDL-C, apolipoprotein B, VLDL-C and TG while increasing HDL-C and apolipoprotein A. The mechanism of action of pravastatin sodium is complex. Inhibition of hepatic VLDL synthesis and/or secretion occurs, leading to a decrease in LDL precursor formation. The reduction in hepatic cellular pools of cholesterol, resulting from the specific and reversible inhibition of HMG-CoA reductase activity, leads to an increase in the fractional catabolic rate of IDL and LDL via increased expression of LDL receptors on the surface of hepatic cells. Through a combination of these and possibly other unknown metabolic effects, a decline in the serum level of cholesterol results.
Cell/Tissue Selective Inhibition of Cholesterol Synthesis
In vitro and animal studies have shown that pravastatin, a hydrophilic HMG-CoA reductase inhibitor, is tissue selective such that inhibitory activity is highest in those tissues with the highest rates of cholesterol synthesis, such as the liver and ileum.
In suspensions of freshly isolated rat hepatocytes and in one-day cultures of rat hepatocytes, pravastatin sodium showed potent inhibition of 14C incorporation into cholesterol. In cultured human skin fibroblasts and other non hepatic cell types, pravastatin inhibited cholesterol synthesis 400 times less than in hepatocytes.
The accumulation of 14C-pravastatin was concentration and time dependent in hepatocytes and barely detectable in fibroblasts.
In tissue slices from rats given oral doses of pravastatin sodium, cholesterol synthesis was inhibited by more than 90% in liver and ileum slices and was substantially lower or not detectable in other tissue slices such as prostate, testes and adrenal.
In the intact rat lens, pravastatin sodium inhibited cholesterol synthesis 10 times less than in liver from the same animals. The inhibition of sterol synthesis in lens epithelial lines derived from the mouse and the rabbit was 400 to 1500 times less than in rat hepatocytes.
Specificity as an Inhibitor of HMG-CoA Reductase
The incorporation of 14C-mevalonate, the product of HMG–CoA reductase reaction into sterols, was not affected in hepatocytes, fibroblasts, or CHO cells at concentrations of pravastatin sodium at least 20 times greater than those that inhibited 14C-acetate incorporation into cholesterol.
At concentrations 500 times greater than those that inhibited acetate incorporation into cholesterol, pravastatin sodium did not alter the rate of incorporation of 14C-acetate into total cell phospholipids in hepatocytes and the distribution of the radiolabel into the separate classes of phospholipids. Pravastatin sodium did not reduce the rate of incorporation of 14C-acetate into triglycerides. These results demonstrate that pravastatin does not act in the sterol pathway at any step beyond the synthesis of mevalonate nor does it inhibit the enzymes required for the biosynthesis of two other major classes of lipids.
The inhibitory activity of pravastatin on the enzyme HMG-CoA reductase was 106 times greater than that demonstrated by pravastatin for HMG-CoA lyase. The active site of this enzyme, which also employs HMG-CoA as substrate, does not recognize pravastatin.
General pharmacology
The effect of pravastatin sodium on major physiologic systems and isolated tissue and its agonist and antagonist effects towards principal neurohumoral transmitters or histamine, behavioral effects, convulsive threshold and tissue- or activity-specific effects were evaluated in animals or in vitro tissue preparations. With the exception of a moderate inhibition of gastric secretion at a dose of 300 mg/kg in rats, pravastatin sodium had no effect in any of these pharmacologic tests at doses of 1000 mg/kg in some species.
10.3 Pharmacokinetics
Absorption
Pravastatin sodium is administered orally in the active form. Following oral ingestion, pravastatin is rapidly absorbed with peak plasma levels attained at about 1 to 1.5 hours. Average oral absorption of pravastatin, based on urinary recovery of radiolabelled drug after oral and intravenous dosing, is 34%; average absolute bioavailability of the parent drug is 17%. The therapeutic response to pravastatin sodium is similar, whether taken with meals or one hour prior to meals, even though the presence of food in the gastrointestinal tract causes a reduction in systemic bioavailability.
| Percent Decrease in LDL–C | ||
|---|---|---|
| Pravastatin | 10 mg bid | 20 mg bid |
| With meals |
|
|
| Before meals * |
|
|
* administered one hour or more prior to eating.
Studies in rats, dogs and humans demonstrated that pravastatin sodium given orally has low bioavailability because of extensive first-pass hepatic extraction. Therefore, most of an oral dose of pravastatin sodium is delivered directly to the liver, the primary site of pharmacologic activity.
Distribution
Pravastatin undergoes extensive first pass extraction in the liver (estimated hepatic extraction ratio, 66%), its primary site of action, and is excreted in the bile. Therefore, plasma levels of the drug are probably of limited value in predicting therapeutic effectiveness. Nevertheless, measurement of plasma pravastatin concentrations by gas chromatography and mass- spectrometry showed dose proportionality for area under the concentration-time curve (AUC) and maximum and steady-state plasma levels. Steady-state areas under the plasma concentration-time curves and maximum (CMAX) or minimum (CMIN) plasma concentrations showed no accumulation following once or twice-daily administration of pravastatin sodium tablets.
A relatively low extent of binding of pravastatin to plasma proteins was found in rats, dogs, monkeys and humans. The highest concentrations of 14C-pravastatin were found in the excretory organs and the GI tract in rats (N=3 to 5), one dog and one monkey. Similar metabolic patterns and appreciable fecal excretion in rats, dogs, monkeys and man were also evident in these studies.
Placental Transfer
Low levels of radioactivity were found in the fetuses of rats dosed orally with radiolabeled pravastatin sodium. Pravastatin sodium was also found to be secreted in the milk of rats.
Metabolism
Pravastatin is extensively metabolized. The major metabolite is the 3 α-hydroxy isomer, which has one-tenth to one-fortieth of the inhibitory activity of the parent compound on HMG-CoA reductase.
Elimination
Protein binding of pravastatin is approximately 50%. The plasma elimination half-life of pravastatin is between 1.5 and 2 hours (2.5 to 3 hours in hypercholesterolemic subjects). Approximately 20% of a radiolabelled oral dose is excreted in the urine and 70% in the feces.
After intravenous administration to healthy subjects, approximately 47% of the total drug clearance occurs via renal excretion of intact pravastatin, and about 53% is cleared by non– renal routes, i.e. biliary excretion and biotransformation.
Dogs are unique as compared to all other species tested, including man, in that they have a much greater systemic exposure to pravastatin. Pharmacokinetic data from a study in dogs at a dose of 1.1 mg/kg (comparable to a 40 mg dose in humans) showed that the elimination of pravastatin is slower in dogs than in humans. Absolute bioavailability is two times greater in dogs compared to humans and estimated renal and hepatic extraction of pravastatin are about one-tenth and one-half, respectively, than those in humans. When concentrations of pravastatin in plasma or serum of rats, dogs, rabbits, monkeys and humans were compared, the exposure in dogs was dramatically higher, based on both CMAX and AUC. The mean AUC value in man at a therapeutic dose of 40 mg is approximately 100 times less than that in the dog at the no-effect dose of 12.5 mg/kg, and approximately 180 times lower than that in dogs at the threshold dose of 25 mg/kg for cerebral hemorrhage.
Special Populations and Conditions
- Pediatrics Only limited experience with the use of statins in children is available. There is no experience to date with the use of pravastatin sodium in such patients. Treatment in these patients is not recommended at this time.
- Geriatrics Studies of pravastatin sodium administered as a single dose to healthy elderly male and female subjects (age 65 to 78 years) indicated a 30 to 50% increase in plasma levels.
- Renal Insufficiency No studies have been carried out in patients with renal insufficiency.
- Storage, Stability, and Disposal
Store at room temperature, 15-30°C. Protect from moisture and light. Keep out of reach and sight of children.
Part 2: Scientific Information
13. Pharmaceutical Information
Drug Substance
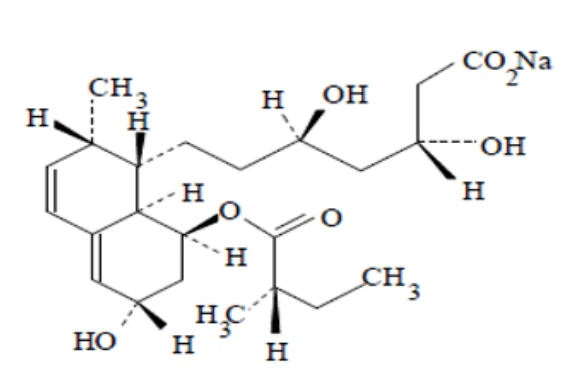
Non-proprietary name of the drug substance: Pravastatin Sodium
Chemical name: Sodium (3R,5R)-3,5-dihydroxy-7-[(1S,2S,6S,8S,8aR)-6-hydroxy-2-methyl-8-[[(2S)-2-methylbutanoyl]oxy]-1,2,6,7,8,8a-hexahydronaphthalen-1-yl]heptanoate
Molecular formula and molecular mass: C23H35O7.Na; 446.5 g/mol
Structural formula:
Physicochemical properties: Pravastatin sodium is a white or yellowish white powder or crystalline powder, hygroscopic. It is freely soluble in water and methanol, soluble in anhydrous ethanol.
14. Clinical Trials
14.1 Clinical Trials by Indication
Hypercholesterolemia
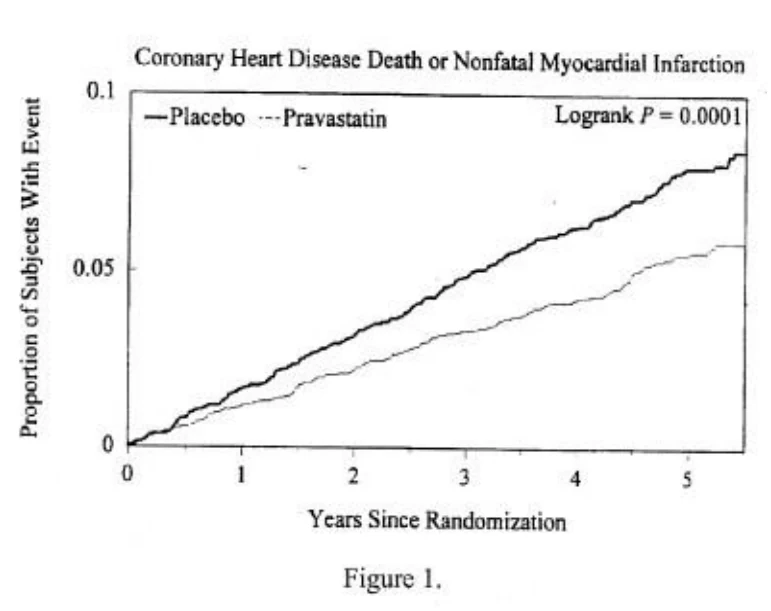
Pravastatin sodium is highly effective in reducing total and LDL cholesterol in patients with primary hypercholesterolemia. A marked response is seen within one week, and the maximum therapeutic response usually occurs within four weeks. The response is maintained during extended periods of therapy. In addition, pravastatin sodium is effective in reducing the progressive cause of atherosclerosis and risk of coronary events, decreasing total mortality, decreasing death due to coronary heart disease, and decreasing the incidence of stroke, in hypercholesterolemic patients with atherosclerotic cardiovascular disease. Pravastatin is also effective in reducing the risk of CHD death (fatal MI and sudden death) plus non-fatal MI with no increase in deaths from non-cardiovascular causes in hypercholesterolemic patients without previous myocardial infarction. Risk reduction is evident within 6 months of the initiation of treatment (see Figure 1).
Single daily doses of pravastatin sodium are effective. As shown in the table which follows, the Total-C and LDL-C lowering effects are the same whether pravastatin sodium is administered in single or divided (bid) doses. Once-daily administration in the evening appears to be marginally more effective than once-daily administration in the morning, perhaps because hepatic cholesterol is synthesized mainly at night.
The results of a multicenter, double-blind regimen response comparative study of placebo and pravastatin, given to parallel groups of patients for 8 weeks are as follows:
Table 5 - Single-Daily Versus Twice-Daily Dosing*
| Pravastatin | N | Total–C | LDL–C | HDL–C | TG |
|---|---|---|---|---|---|
| 40 mg qam | 41 |
|
| + 4% |
|
| 40 mg qpm | 33 |
|
| + 8% |
|
| 20 mg bid | 44 |
|
| + 8% |
|
*Evening doses were administered at least 3 hours after the evening meal. Morning doses were administered at least 1 hour prior to breakfast.
Patients with primary hypercholesterolemia (71% Familial or Familial Combined, 29% Non- Familial). Baseline mean LDL-C = 6.34 mmol/L (245.4 mg/dL).
In multicenter, double-blind studies of patients with primary hypercholesterolemia, pravastatin sodium administered in daily doses ranging from 5 mg to 80 mg to over 1100 patients was compared with placebo. Pravastatin significantly decreased Total-C and LDL-C levels, and Total- C/HDL-C and LDL-C/HDL-C ratios. In addition, pravastatin slightly increased HDL-C and decreased VLDL-C and plasma TG levels.
Dose-response effects on lipids from two studies evaluated after 8 weeks of administering pravastatin sodium once or twice-daily are illustrated in the tables below.
Table 6 - Dose-Response Results* (Once-Daily Administration at Bedtime)
| Pravastatin | N | Total-C | LDL-C | HDL-C | TG |
|---|---|---|---|---|---|
| 5 mg qd | 16 |
|
| + 5% |
|
| 10 mg qd | 18 |
|
| + 7% |
|
| 20 mg qd | 19 |
|
| + 2% |
|
| 40 mg qd | 18 |
|
| + 12% |
|
*Patients with primary hypercholesterolemia (28% Familial or Familial Combined, 72% Non-Familial). Baseline mean LDL-C = 5.68 mmol/L (219.6 mg/dL).
Table 7 - Dose-Response Results * (BID Administration)
| Pravastatin | N | Total-C | LDL-C | HDL-C | TG |
|---|---|---|---|---|---|
| 5 mg bid | 59 |
|
| +7% |
|
| 10 mg bid | 53 |
|
| + 6% |
|
| 20 mg bid | 56 |
|
| + 5% |
|
*Patients with primary hypercholesterolemia (70% Familial or Familial Combined, 30% Non-Familial). Baseline mean LDL–C = 6.06 mmol/L (234.5 mg/dL).
Pravastatin sodium is also effective when given with a bile acid-binding resin. In a study of pravastatin sodium administered alone or in combination with cholestyramine, marked reductions in the level of LDL-C were observed. In addition, pravastatin sodium attenuated the increase in TG levels observed with cholestyramine alone (The results of the study cited in the table which follows should be interpreted in the context of the exceptionally high rate of patient compliance with the bile acid-binding resin [70% of patients were taking 20 or 24 g daily]).
Table 8 - Comparison with Cholestyramine Resin*
| N | Total–C | LDL–C | HDL–C | TG | |||||||
|---|---|---|---|---|---|---|---|---|---|---|---|
| N | Total–C | LDL–C | HDL–C | TG | |||||||
| Pravastatin | |||||||||||
| 20 mg bid | 49 |
|
| + 6% |
| ||||||
| 40 mg bid | 52 |
|
| + 5% |
| ||||||
| Resin Alone ** | 41 |
|
| + 2% | + 16% | ||||||
| Combination | |||||||||||
20 mg bid & Resin ** | 49 |
|
| + 5% |
| ||||||
*Patients with primary hypercholesterolemia (68% Familial or Familial Combined; 32% Non-Familial). Baseline mean LDL–C = 6.09 mmol/L (235.3 mg/dL).
**The dose of resin used in this study was 24 g.
Primary Prevention of Coronary Events
Pravastatin sodium has been shown to be effective in reducing the risk of coronary heart disease (CHD) death plus non-fatal MI in hypercholesterolemic patients without previous myocardial infarction.
In the West of Scotland Study (WOS), the effect of pravastatin sodium on fatal and non-fatal coronary heart disease (CHD) was assessed in 6595 patients. The patient population consisted of men 45 to 64 years of age, without a previous MI, and with LDL-C levels between 4 to 6.7 mmol/L (156 to 254 mg/dL). In this randomized, double-blind, placebo-controlled study, patients were treated with standard care, including dietary advice, and either pravastatin sodium 40 mg daily (n = 3302) or placebo (n = 3293) for a median duration of 4.8 years.
Pravastatin sodium significantly reduced the risk of CHD death plus non-fatal MI by 31% (248 patients in the placebo group [CHD death = 44, non-fatal MI = 204] vs 174 patients in the pravastatin sodium group [CHD death = 31, non-fatal MI = 143], p = 0.0001). As shown in the figure below, divergence in the cumulative event rate curves for this endpoint begins within 6 months of treatment. This reduction was similar and significant throughout the entire range of baseline LDL cholesterol levels with a 37% risk reduction for LDL cholesterol 4 to 4.8 mmol/L (156 to188 mg/dL) (p = 0.003) and a 27% risk reduction for LDL cholesterol 4.9 to 6.7 mmoI/L (189 to 254 mg/dL) (p = 0.03). This reduction was also similar and significant for all age groups studied with a 40% risk reduction for patients younger than 55 years (p = 0.002) and 27% risk reduction for patients 55 years and older (p = 0.009).
Total cardiovascular deaths were reduced by 32% (73 vs 50, p = 0.03) and overall mortality by 22% (135 vs 106, p = 0.051). There was no statistically significant difference between treatment groups in non-cardiovascular mortality, including cancer deaths. Pravastatin sodium also decreased the risk for undergoing myocardial revascularization procedures (coronary artery bypass graft surgery or coronary angioplasty) by 37% (80 vs 51 patients, p = 0.009) and coronary angiography by 31% (128 vs 90, p = 0.007).
The West of Scotland Study excluded female patients, elderly subjects and most patients with familial hypercholesterolemia (FH). Consequently it has not been established to what extent the findings of the WOS study can be extrapolated to these subpopulations of hypercholesterolemic patients.
- In patients with heterozygous FH, optimal reduction in total and LDL cholesterol necessitates a combination drug therapy in the majority of patients, (For homozygous FH see 7 Warnings and Precautions, General).
- Because information on familial combined hyperlipidemic (FCH) patients is not available from the WOS study, the effect of pravastatin sodium in this subgroup of high risk dyslipidemic patients could not be assessed.
Secondary Prevention of Cardiovascular Events
Pravastatin sodium has been shown to be effective in reducing the risk for total mortality, CHD death, recurrent coronary events (including myocardial infarction), frequency of stroke or transient ischemic attacks (TIA), need for myocardial revascularization procedures, and need for hospitalization in patients with a history of either myocardial infarction or unstable angina pectoris.
In the Long-Term Intervention with Pravastatin in Ischemic Disease (LIPID) study, the effect of pravastatin sodium 40 mg daily was assessed in 9014 men and women with normal to elevated serum cholesterol levels (baseline Total-C=155 to 271 mg/dL [4.0 to7.0 mmol/L]; median Total- C=218 mg/dL [5.66 mmol/L]; median LDL-C=150 mg/dL [3.88 mmol/L]), and who had experienced either a myocardial infarction or had been hospitalized for unstable angina pectoris in the preceding 3 to 36 months. Patients with a wide range of baseline levels of triglycerides were included (≤443 mg/dL [5.0 mmol/L]) and enrollment was not restricted by baseline levels of HDL cholesterol. At baseline, 82% of patients were receiving aspirin, 47% were receiving beta blockers, and 76% were receiving antihypertensive medication. Patients in this multicenter, double-blind, placebo-controlled study participated for a mean of 5.6 years (median=5.9 years).
Treatment with pravastatin sodium significantly reduced the risk for CHD death by 24% (p=0.0004). The risk for coronary events (either CHD death or nonfatal MI) was significantly reduced by 24% (p<0.0001) in the pravastatin sodium treated patients. The risk for fatal or nonfatal myocardial infarction was reduced by 29% (p<0.0001). Pravastatin sodium reduced both the risk for total mortality by 23% (p<0.0001) and cardiovascular mortality by 25% (p<0.0001). The risk for undergoing myocardial revascularization procedures (coronary artery bypass grafting or percutaneous transluminal coronary angioplasty) was significantly reduced by 20% (p<0.0001) in the pravastatin sodium treated patients. Pravastatin sodium also significantly reduced the risk for stroke by 19% (p = 0.0477). Treatment with pravastatin sodium significantly reduced the number of days of hospitalization per 100 person-years of follow-up by 15% (p<0.001). The effect of pravastatin sodium on reducing CHD events was consistent regardless of age, gender, or diabetic status. Among patients who qualified with a history of myocardial infarction, pravastatin sodium significantly reduced the risk for total mortality and for fatal or non-fatal MI (risk reduction for total mortality 21%, p = 0.0016; risk reduction for fatal or nonfatal MI=25%, p = 0.0008). Among patients who qualified with a history of hospitalization for unstable angina pectoris, pravastatin sodium significantly reduced the risk for total mortality and for fatal or non-fatal MI (risk reduction for total mortality = 26%, p = 0.0035; risk reduction for fatal or non-fatal MI=37%, p = 0.0003).
In the Cholesterol and Recurrent Events (CARE) study the effect of pravastatin sodium 40 mg daily on coronary heart disease death and nonfatal MI was assessed in 4159 men and women with normal serum cholesterol levels (baseline mean Total-C=209 mg/dL [5.4 mmol/L]), and who had experienced a myocardial infarction in the preceding 3 to 20 months. At baseline, 83% of patients were receiving aspirin, 55% had undergone PTCA/CABG, 40% were receiving beta blockers, and 82% were receiving antihypertensive medication. Patients in this double-blind, placebo-controlled study participated for an average of 4.9 years. Treatment with pravastatin sodium significantly reduced the rate of a recurrent coronary event (either CHD death or nonfatal MI) by 24% (274 patients with events [13.3%] in the placebo group vs. 212 patients [10.4%] in the pravastatin sodium group, p=0.003). The reduction in risk for this combined endpoint was significant for both men and women; in women, the reduction in risk was 43% (p=0.033). The risk of undergoing revascularization procedures (coronary artery bypass grafting or percutaneous transluminal coronary angioplasty) was significantly reduced by 27% (p<0.001) in the pravastatin treated patients (391 [19.6%] vs 294 [14.2%] patients). Pravastatin sodium also significantly reduced the risk for stroke by 32% (p=0.032), and stroke or transient ischemic attack (TIA) combined by 26% (124 [6.3%] vs 93 [4.7%] patients, p=0.025).
Atherosclerotic Disease Progression
In two controlled trials [PLAC I, PLAC II] in patients with moderate hypercholesterolemia and atherosclerotic cardiovascular disease, pravastatin was effective in reducing the progressive course of atherosclerosis as evaluated by quantitative angiography and B-mode ultrasound. This effect may be associated with an improvement in the coronary endpoints (fatal or non-fatal MI). No difference in total mortality was detected during the 3 years of double-blind therapy.
In PLAC I (Pravastatin Limitation of Atherosclerosis in the Coronary Arteries), a 3-year, placebo- controlled, multicentre, randomized trial of 408 patients with moderate hypercholesterolemia (baseline LDL–C range = 3.37 to 4.92 mmol/L (130 to 190 mg/dL)) and coronary artery disease, treatment with pravastatin reduced the rate of narrowing of the coronary artery lumen diameter as determined by quantitative angiography. The analyses of clinical cardiovascular events showed a favourable effect of pravastatin therapy on events that occurred > 90 days after randomization, as well as for events from the time of randomization. This effect was not accompanied by an improvement in the total mortality endpoint. In PLAC II (Pravastatin Lipids and Atherosclerosis in the Carotid Arteries), a 3-year, placebo-controlled trial, in 151 patients with moderate hypercholesterolemia (baseline LDL-C range = 3.76 to 4.92 mmol/L (145 to 190 mg/dL)) and coronary and carotid atherosclerosis, treatment with pravastatin significantly reduced the rate of progression of atherosclerosis in common carotid artery, as measured by B- mode ultrasound. The rate of progression of the mean-maximum intimal-medial thickness (IMT) was not significantly reduced. There was a decrease in the incidence of coronary events of borderline significance. No difference in total mortality was observed during the 3 years of double-blind therapy.
Solid Organ Transplant
Myopathy has not been observed in clinical trials involving a total of 100 post-transplant patients (76 cardiac and 24 renal) treated concurrently for two years with pravastatin (10 to 40 mg) and cyclosporine some of whom also received other immunosuppressants. Further, in clinical trials involving small numbers of patients treated with pravastatin, together with niacin, there were no reports of myopathy.
14.2 Comparative Bioavailability Studies
A randomized, balanced, double blinded, two-treatment, two-period, two-sequence, single-dose, crossover, bioequivalence study of PrAG-Pravastatin Tablets 40 mg, tablets (Angita Pharma Inc.) and PrAPO-PRAVASTATIN 40 mg, tablets (Apotex Inc.) was conducted in healthy, adult, human subjects under fasting conditions.
A summary of the bioavailability data from the 32 subjects is presented in the following table:
SUMMARY TABLE OF THE COMPARATIVE BIOAVAILABILITY DATA
Pravastatin (1 x 40 mg Tablet) Geometric Mean Arithmetic Mean (CV %) | ||||
| Parameter | Test1 | Reference2 | % Ratio of Geometric Means | 90% Confidence Interval |
AUCT (ng.h/ml) | 236.28 279.87 (51.0) | 224.94 257.00 (47.4) | 105.0 | 94.4 - 116.9 |
AUCI (ng.h/ml) | 243.71 285.73 (49.7) | 231.89 262.59 (46.2) | 105.1 | 95.0 - 116.3 |
Cmax (ng/ml) | 91.06 116.77 (60.6) | 86.00 102.79 (55.0) | 105.9 | 90.1 - 124.5 |
Tmax3 (h) | 1.00 (0.75 - 2.33) | 1.00 (0.75 - 2.33) | ||
T1/24 (h) | 2.01 (28.2) | 1.99 (24.4) | ||
1 PrAG-Pravastatin Tablets (as pravastatin sodium) tablets, 40 mg (Angita Pharma Inc.)
2 PrAPO-PRAVASTATIN (as pravastatin sodium) tablets, 40 mg (Apotex Inc.)
3 Expressed as the median (range) only
4 Expressed as the arithmetic mean (CV%)
16. Non-Clinical Toxicology
General toxicology
Acute Toxicity
Table 10 – Acute Toxicity
| Species | Sex (N) | Route | LD50 (mg/kg) |
|---|---|---|---|
| Species | Sex (N) | Route | LD50 (mg/kg) |
| Mouse | M (50) F (50) | Oral | 10590 8939 |
| Mouse | M (50) F (50) | i.v. | 2114 2011 |
| Mouse | M (50) F (50) | s.c. | 2975 3667 |
| Rat | M (20) F (20) | Oral | > 12000 > 12000 |
| Rat | M (50) F (50) | i.v. | 443 440 |
| Rat | M (50) F (50) | s.c. | 3172 4455 |
| Dog | M (4) | Oral | > 800 |
Signs of toxicity in mice were decreased activity, irregular respiration, ptosis, lacrimation, soft stool, diarrhea, urine-stained abdomen, ataxia, creeping behavior, loss of righting reflex, hypothermia, urinary incontinence, pilo-erection convulsion and/or prostration.
Signs of toxicity in rats were soft stool, diarrhea, decreased activity, irregular respiration, waddling gait, ataxia, loss of righting reflex and/or weight loss.
Subacute and Chronic Toxicity
The spectrum of effects produced by pravastatin in mice, rats, rabbits, dogs and monkeys shown on the following table is not unexpected in view of the magnitude of the dosage levels employed and the potency of pravastatin against the HMG-CoA reductase.
Table 11 - Target Organs Observed In Animal Studies
| Organ | Mouse | Rat | Rabbit | Dog | Monkey |
|---|---|---|---|---|---|
| Liver, neoplastic effect | - | + | - | - | - |
| Liver, non-neoplastic effect | + | + | + | - | + |
| Kidney | - | - | + | - | + |
| Skeletal muscle | - | + | + | - | - |
| Brain | - | - | - | + | - |
+ = Organ affected in some way by drug treatment
- = No effect observed in this organ in these species
On a mg/kg basis, rabbits appear to be more sensitive to the nephrotoxic effects of pravastatin sodium than monkeys, the only other species that exhibited renal toxicity. In rabbits, renal dysfunction and hepatic effects were observed at doses ≥ 25 mg/kg/day. In monkeys, hepatotoxicity and nephrotoxicity occurred at doses of 100 mg/kg/day. The threshold dose for renal toxicity in rabbits is 31 times greater than the maximum human dose.
Table 12 - Significant Adverse Changes
| Pravastatin | ||||||
|---|---|---|---|---|---|---|
| Pravastatin | ||||||
Minimal Toxic Dose (mg/kg/day) | No-Effect Dose (mg/kg/day) | |||||
Minimal Toxic Dose (mg/kg/day) | No-Effect Dose (mg/kg/day) | |||||
| Mice | ||||||
| Single-cell necrosis in the liver | 40 | 20 | ||||
| Elevated serum transaminase activity | 20 | 10 | ||||
| Rats | ||||||
| Hepatic tumors | 100 | 40 | ||||
| Foci of hepato-cellular alteration | 30 | 12 | ||||
| Elevated transaminase activity | 100 | 50 | ||||
| Skeletal-muscle myolysis | 400 | 250 | ||||
| Rabbits | ||||||
| Death | 400 | 100 | ||||
| Hepatocellular necrosis | 100 | 25 | ||||
| Renal tubular degeneration | 25 | 6.25 | ||||
| Skeletal-muscle myolysis | 100 | 25 | ||||
| Elevated serum transaminase activity | 100 | 25 | ||||
| Dogs | ||||||
| Death | 25 | 12.5 | ||||
| Cerebral hemorrhage | 25 | 12.5 | ||||
| Monkeys | ||||||
| Death | 200 | 100 | ||||
| Hepatocellular necrosis | 100 | 50 | ||||
| Renal tubular degeneration | 100 | 50 | ||||
| Elevated serum transaminase activity | 100 | 50 | ||||
Noteworthy findings in these studies included varying degrees of hepatotoxicity in all species tested, renal toxicity in rabbits and monkeys, skeletal-muscle lesions in rabbits, CNS symptoms and death secondary to cerebral hemorrhage in dogs, and an increased incidence of hepatic lesions and evidence of hepatocarcinoma (the latter at 100 mg/kg) in rats treated for 2 years. In all cases, these changes occurred only at daily doses of 20 mg/kg or more (more than 25 times the maximum human dose).
The findings from the chronic toxicity in dogs are detailed on the following pages.
Table 13 – Chronic Toxicity
Species/ Strain | Sex | N/Dose | Dose (mg/kg/day) | Route | Time | Effects | ||||||||||||||
|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|
| Subacute Toxicity | ||||||||||||||||||||
| Dog | M | 3 | 0, 12.5, 50 or | Oral | 5 weeks | 200 mg/kg: One dog died and 4 dogs | ||||||||||||||
| Beagle | F | 3 | 200 | (capsule) | sacrificed on days 11 to 22 after | |||||||||||||||
| exhibiting ataxia and/or convulsions, | ||||||||||||||||||||
| salivation, urinary incontinence | ||||||||||||||||||||
| and/or defecation. Ecchymotic | ||||||||||||||||||||
| lesions (hemorrhagic foci) in the | ||||||||||||||||||||
| brain. | ||||||||||||||||||||
| Dog | M | 6 | 0 or 100 | Oral | 13 | 100 mg/kg: One death (F) on day 42 | ||||||||||||||
| Beagle | F | 6 | (2M, 2F | (capsule) | weeks | preceded by marked decrease in | ||||||||||||||
| controls) | activity, serous salivation and | |||||||||||||||||||
| (4M, 4F | vomiting. Diapedetic hemorrhage | |||||||||||||||||||
| treated) | and degeneration of venular | |||||||||||||||||||
| endothelial cells in one F and the F that died. | ||||||||||||||||||||
| Chronic Toxicity | ||||||||||||||||||||
Dog Beagle | M F | 4M, 4F at 12.5 & 25
at 0, 50 & 100 | 0, 12.5, 25, 50 or 100 | Oral (capsule) | 2 years | 25 mg/kg: Two F sacrificed during weeks 60 and 61. One had lesions consistent with idiopathic coagulopathy. The other showed clinical signs of CNS toxicity prior to sacrifice and had brain lesions.1 50 mg/kg: All dogs showed clinical signs of CNS toxicity; 5/6 dogs had brain lesions.1 100 mg/kg: Three M and 5 F died or sacrificed between weeks 2 and 24. One M died in week 76. All dogs showed clinical signs of CNS toxicity prior to death/sacrifice. Nine/nine dogs had brain lesions. | ||||||||||||||
1Brain lesions (primarily in the piriform lobes) were characterized by discrete multifocal perivascular capillary and venular hemorrhages. In more severe lesions, there was an increased number of focal perivascular hemorrhages and associated early degenerative neutrophil changes including vacuolization, edema, and mild neutrophil infiltration. Larger vascular elements were not involved. No vascular endothelial changes were present, based on light- and electron-microscopic studies.
Chronic Toxicity (cont’d)
In dogs, pravastatin sodium was toxic at high doses and caused cerebral hemorrhage with clinical evidence of acute CNS toxicity (e.g. ataxia, convulsions). A dose-response relationship with respect to the incidence of CNS toxicity was clearly evident. In dogs, the threshold dose for
CNS toxicity is 25 mg/kg. The high systemic exposure to orally administered pravastatin in dogs (refer to 10.3 Pharmacokinetics) may be related to a greater bioavailability and slower elimination of pravastatin and likely plays an important role in the development of CNS lesions that occur in the dog.
Cerebral hemorrhages have not been observed to date in any other laboratory species and the CNS toxicity in dogs may represent a species-specific effect.
Carcinogenicity
In mice and rats, treated for 21 months with oral doses approximately 12 and 25 times the maximum human dose respectively (i.e. 20 mg/kg daily and 40 mg/kg daily), pravastatin sodium was found to be non carcinogenic. After 86 and 104 weeks of dosing in mice and rats respectively, at oral doses approximately 60 times the maximum human dose (i.e. 100 mg/kg daily), statistically significant increases in the incidence of hepatocellular carcinoma were observed in male rats only.
In in vivo mutagenicity tests with i.p. doses up to 1400 mg/kg and in in vitro mutagenicity tests at concentrations up to 10000 mcg/mL or plate, pravastatin sodium was found to be nonmutagenic.
Pravastatin was found to be non-genotoxic.
Reproductive and developmental toxicology
Aside from a slight maternal toxicity in rabbits at 50 mg/kg and in rats at 1000 mg/kg, there were no treatment-related findings.
In rabbits and rats at doses greater than 60 and 600 times respectively the maximum human dose, pravastatin sodium exerted no untoward effects on reproduction through the F1 generation in rats and did not cause any fetal or anatomic abnormalities through the F1 generation in rabbits and the F2 generation rats.
17. Supporting Product Monographs
- 1) PrPravachol® (pravastatin sodium tablets, 20 mg and 40 mg), control 234107, product monograph, Bristol-Myers Squibb Canada. (2020-03-04)
- 2) PrAPO-PRAVASTATIN (Tablets, 10 mg, 20 mg and 40 mg), control 294008, product monograph, Apotex Inc. 2025-07-24