


Product Monograph - Apo-Abiraterone Acetate Film Coated Tablets
SUMMARY PRODUCT INFORMATION
| Route of Administration | Dosage Form / Strength | Clinically Relevant Nonmedicinal Ingredients |
| Oral | Film-coated Tablet 500 mg | Tablet Core: colloidal silicon dioxide, crospovidone, lactose monohydrate, magnesium stearate, microcrystalline cellulose and sodium lauryl sulfate. Film-coating: ferric oxide red, iron oxide black, polyethylene glycol, polyvinyl alcohol, talc and titanium dioxide. |
INDICATIONS AND CLINICAL USE
APO-ABIRATERONE ACETATE FILM COATED TABLETS (abiraterone acetate) is indicated in combination with prednisone for the treatment of metastatic prostate cancer (castration-resistant prostate cancer, mCRPC) in patients who:
- are asymptomatic or mildly symptomatic after failure of androgen deprivation therapy
- have received prior chemotherapy containing docetaxel after failure of androgen deprivation therapy
APO-ABIRATERONE ACETATE FILM COATED TABLETS is also indicated in combination with prednisone and androgen deprivation therapy (ADT) for the treatment of patients with newly diagnosed hormone-sensitive high-risk metastatic prostate cancer who may have received up to 3 months of prior ADT.
Geriatrics (≥ 65 years of age):
In the Phase 3 studies of abiraterone acetate 70% of patients were 65 years and over, and 27% of patients were 75 years and over. No overall differences in safety or effectiveness were observed between these elderly patients and younger patients (see WARNINGS AND PRECAUTIONS, Special Populations, Geriatrics).
Pediatrics:
Abiraterone acetate has not been studied in children.
CONTRAINDICATIONS
- Patients who are hypersensitive to this drug or to any ingredient in the formulation or component of the container (See WARNINGS AND PRECAUTIONS/ Hypersensitivity/Anaphylactic reaction).
- For a complete listing, see the DOSAGE FORMS, COMPOSITION AND PACKAGING section of the Product Monograph.
- Women who are or may potentially be pregnant.
WARNINGS AND PRECAUTIONS
Serious Warnings and Precautions
|
General
Gonadotropin releasing hormone (GnRH) agonists must be taken during treatment with APO-ABIRATERONE ACETATE FILM COATED TABLETS or patients must have been previously treated with orchiectomy.
APO-ABIRATERONE ACETATE FILM COATED TABLETS must be taken on an empty stomach. No solid or liquid food should be consumed for at least two hours before the dose of APO-ABIRATERONE ACETATE FILM COATED TABLETS is taken and for at least one hour after the dose of APO-ABIRATERONE ACETATE FILM COATED TABLETS is taken. Abiraterone Cmax and AUC0-∞ (exposure) were increased up to 17- and 10-fold higher, respectively, when a single dose of abiraterone acetate was administered with a meal compared to a fasted state. The safety of these increased exposures when multiple doses of abiraterone acetate are taken with food has not been assessed (see DRUG INTERACTIONS Drug-Food Interactions, DOSAGE AND ADMINISTRATION, and ACTION AND CLINICAL PHARMACOLOGY).
Reproductive Toxicology
In fertility studies in both male and female rats, abiraterone acetate reduced fertility, which was completely reversible in 4 to 16 weeks after abiraterone acetate was stopped. In a developmental toxicity study in the rat, abiraterone acetate affected pregnancy including reduced fetal weight and survival. Effects on the external genitalia were observed though abiraterone acetate was not teratogenic. In these fertility and developmental toxicity studies performed in the rat, all effects were related to the pharmacological activity of abiraterone (see TOXICOLOGY, Reproductive Toxicology).
Carcinogenesis and Mutagenesis
Abiraterone acetate was not carcinogenic in a 6-month study in the transgenic (Tg.rasH2) mouse. In a 24-month carcinogenicity study in the rat, abiraterone acetate increased the incidence of interstitial cell neoplasms in the testes. This finding is considered related to the pharmacological action of abiraterone. The clinical relevance of this finding is not known. Abiraterone acetate was not carcinogenic in female rats (see TOXICOLOGY, Carcinogenesis and Genotoxicity).
Abiraterone acetate and abiraterone were devoid of genotoxic potential in the standard panel of in vitro and in vivo genotoxicity tests (see TOXICOLOGY, Carcinogenesis and Genotoxicity).
Cardiovascular
APO-ABIRATERONE ACETATE FILM COATED TABLETS should be used with caution in patients with a history of cardiovascular disease. The safety of Abiraterone acetate in patients with myocardial infarction, or arterial thrombotic events in the past 6 months, severe or unstable angina, or left ventricular ejection fraction (LVEF) <50% or New York Heart Association Class III or IV heart failure (in patients with mCRPC with prior treatment with docetaxel) or NYHA Class II to IV heart failure (in patients with asymptomatic or mildly symptomatic mCRPC, or newly diagnosed high-risk metastatic prostate cancer) has not been established because these patients were excluded from the pivotal studies.
Hypertension, Hypokalemia and Fluid Retention Due to Mineralocorticoid Excess
Before treatment with APO-ABIRATERONE ACETATE FILM COATED TABLETS, hypertension must be controlled, and hypokalemia must be corrected.
APO-ABIRATERONE ACETATE FILM COATED TABLETS may cause hypertension, hypokalemia and fluid retention (see ADVERSE REACTIONS) as a consequence of increased mineralocorticoid levels resulting from CYP17 inhibition (see ACTION AND CLINICAL PHARMACOLOGY, Mechanism of Action). Co-administration of a corticosteroid suppresses adrenocorticotropic hormone (ACTH) drive, resulting in a reduction in the incidence and severity of these adverse reactions. Caution is required in treating patients whose underlying medical conditions might be compromised by potential increases in blood pressure, hypokalemia or fluid retention, e.g., those with heart failure, recent myocardial infarction or ventricular arrhythmia. In post marketing experience, QT prolongation and Torsades de Pointes have been observed in patients who develop hypokalemia or have underlying cardiovascular conditions while taking abiraterone acetate. Blood pressure, serum potassium and fluid retention should be monitored at least monthly (see Monitoring and Laboratory Tests).
Corticosteroid Withdrawal and Coverage of Stress Situations
Caution is advised if patients need to be withdrawn from prednisone. Monitoring for adrenocortical insufficiency should occur. If APO-ABIRATERONE ACETATE FILM COATED TABLETS is continued after corticosteroids are withdrawn, patients should be monitored for symptoms of mineralocorticoid excess.
In patients on prednisone who are subjected to unusual stress (e.g., surgery, trauma or severe infections), increased dosage of a corticosteroid may be indicated before, during and after the stressful situation.
Hepatic
Hepatic impairment
APO-ABIRATERONE ACETATE FILM COATED TABLETS should not be used in patients with pre-existing moderate or severe hepatic impairment (see WARNINGS AND PRECAUTIONS, Special Populations, and Monitoring and Laboratory Tests, and ACTION AND CLINICAL PHARMACOLOGY).
Hepatotoxicity
Cases of acute liver failure and hepatitis fulminant (including fatal outcomes) have been reported during post-marketing experience (see WARNINGS AND PRECAUTIONS, Serious Warnings and Precautions, and ADVERSE REACTIONS, Post-Market Adverse Drug Reactions).
Marked increases in liver enzymes leading to drug discontinuation or dosage modification occurred in controlled clinical studies (see ADVERSE REACTIONS). Serum transaminases (ALT and AST) and bilirubin levels should be measured prior to starting treatment with APO-ABIRATERONE ACETATE FILM COATED TABLETS, every two weeks for the first three months of treatment, and monthly thereafter. Promptly measure serum total bilirubin and serum transaminases (ALT and AST), if clinical symptoms or signs suggestive of hepatotoxicity develop. If at any time the serum transaminases (ALT or AST) rise above 5 times the upper limit of normal or the bilirubin rises above 3 times the upper limit of normal, treatment with APO-ABIRATERONE ACETATE FILM COATED TABLETS should be interrupted immediately and liver function closely monitored.
Re-treatment with APO-ABIRATERONE ACETATE FILM COATED TABLETS may only take place after the return of liver function tests to the patient’s baseline and at a reduced dose level (see DOSAGE AND ADMINSTRATION).
Permanently discontinue APO-ABIRATERONE ACETATE FILM COATED TABLETS for patients who develop a concurrent elevation of ALT greater than 3 times the upper limit of normal and total bilirubin greater than 2 times the upper limit of normal in the absence of biliary obstruction or other causes responsible for the concurrent elevation (see DOSAGE AND ADMINISTRATION).
If patients develop severe hepatotoxicity (ALT or AST 20 times the upper limit of normal) anytime while on therapy, APO-ABIRATERONE ACETATE FILM COATED TABLETS should be discontinued and patients should not be re- treated with APO-ABIRATERONE ACETATE FILM COATED TABLETS.
Endocrine and Metabolism
Hypoglycemia
Isolated cases of hypoglycemia have been reported when APO-ABIRATERONE ACETATE FILM COATED TABLETS plus prednisone/prednisolone was administered to patients with pre-existing diabetes receiving pioglitazone or repaglinide (see DRUG INTERACTIONS). Blood glucose should be monitored in patients with diabetes.
Hypersensitivity/Anaphylactic reaction
Cases of anaphylactic reactions (severe allergic reactions that include, but are not limited to, difficulty swallowing or breathing, swollen face, lips, tongue or throat, or an itchy rash (urticaria)) requiring rapid medical interventions, have been reported during post-marketing experience (See CONTRAINDICATIONS and ADVERSE REACTIONS/Post-Market Adverse Drug Reactions).
Use with Chemotherapy
The safety and efficacy of concomitant use of abiraterone acetate with cytotoxic chemotherapy has not been established.
Use in Combination with radium 223 dichloride
In a randomized clinical trial in patients with asymptomatic or mildly symptomatic bone- predominant metastatic castration resistant prostate cancer with bone metastases, the addition of radium 223 dichloride to abiraterone acetate plus prednisone/prednisolone showed an increase in mortality and an increased rate of fracture. Radium 223 dichloride is not recommended for use in combination with abiraterone acetate plus prednisone/prednisolone outside of clinical trials.
Skeletal Muscle Effects
Cases of myopathy have been reported in patients treated with abiraterone acetate. Some patients had rhabdomyolysis with renal failure. Most cases developed within the first month of treatment and recovered after abiraterone acetate withdrawal. Caution is recommended in patients concomitantly treated with drugs known to be associated with myopathy/rhabdomyolysis.
Special Populations
Pregnant Women: APO-ABIRATERONE ACETATE FILM COATED TABLETS is contraindicated in women who are or may potentially be pregnant (see CONTRAINDICATIONS and TOXICOLOGY, Reproductive Toxicology).
There are no human data on the use of abiraterone acetate in pregnancy and APO-ABIRATERONE ACETATE FILM COATED TABLETS is not for use in women of child-bearing potential. Maternal use of a CYP17 inhibitor is expected to produce changes in hormone levels that could affect development of the fetus (see CONTRAINDICATIONS). Based on animal studies, there is potential of fetal harm (see TOXICOLOGY, Reproductive Toxicology).
It is not known if abiraterone or its metabolites are present in semen. A condom is required if the patient is engaged in sexual activity with a pregnant woman. If the patient is engaged in sex with a woman of child-bearing potential, a condom is required along with another effective contraceptive method. These measures are required during and for one week after treatment with APO-ABIRATERONE ACETATE FILM COATED TABLETS.
To avoid inadvertent exposure, women who are pregnant or women who may be pregnant should not handle APO-ABIRATERONE ACETATE FILM COATED TABLETS without protection, e.g., gloves.
Nursing Women: APO-ABIRATERONE ACETATE FILM COATED TABLETS is not for use in women. It is not known if either abiraterone acetate or its metabolites are excreted in human breast milk.
Pediatrics (< 18 years of age): Abiraterone acetate has not been studied in children.
Geriatrics (> 65 years of age): In the Phase 3 studies of abiraterone acetate, 70% of patients were 65 years and over, and 27% of patients were 75 years and over. No overall differences in safety or effectiveness were observed between these elderly patients and younger patients.
Patients with Hepatic Impairment: Patients with pre-existing moderate or severe hepatic impairment should not receive APO-ABIRATERONE ACETATE FILM COATED TABLETS. Abiraterone acetate has not been studied in mCRPC patients with moderate or severe (Child-Pugh Class B or C) hepatic impairment at baseline. For patients who develop hepatotoxicity during treatment, suspension of treatment and dosage adjustment may be required (see WARNINGS AND PRECAUTIONS, DOSAGE AND ADMINISTRATION and ACTION AND CLINICAL PHARMACOLOGY, Special Populations and Conditions).
Patients with Renal Impairment: No dosage adjustment is necessary for patients with renal impairment (see DOSAGE AND ADMINISTRATION).
Monitoring and Laboratory Tests
Serum transaminases and bilirubin should be measured prior to starting treatment with APO-ABIRATERONE ACETATE FILM COATED TABLETS, every two weeks for the first three months of treatment and monthly thereafter.
Blood pressure, serum potassium and fluid retention should be monitored monthly (see WARNINGS AND PRECAUTIONS). For patients taking 5 mg/day of prednisone, if hypokalemia persists despite optimal potassium supplementation and adequate oral intake, or if any of the other mineralocorticoid effects persist, the dose of prednisone may be increased to 10 mg/day.
Caution is advised if patients need to be withdrawn from prednisone. Monitoring for adrenocortical insufficiency should occur. If APO-ABIRATERONE ACETATE FILM COATED TABLETS is continued after corticosteroids are withdrawn, patients should be monitored for symptoms of mineralocorticoid excess (see WARNINGS AND PRECAUTIONS, Corticosteroid Withdrawal and Coverage of Stress Situations).
Blood glucose levels should be monitored in patients with pre-existing diabetes receiving concomitant medications such as repaglinide or pioglitazone (see WARNINGS AND PRECAUTIONS, Endocrine and Metabolism, Hypoglycemia).
ADVERSE REACTIONS
Adverse Drug Reaction Overview
In combined data from Phase 3 trials, the adverse reactions seen with abiraterone acetate in ≥10% of patients were hypertension (21%), peripheral edema (19%), hypokalemia (18%), and alanine aminotransferase (ALT) increased and/or aspartate aminotransferase (AST) increased (13%).
The most common adverse reactions leading to dose interruption, reduction, or other modification in patients treated with abiraterone acetate versus placebo were hypokalemia (3% vs. 1%), hypertension (3% vs. 1%), AST elevation (2% vs. 1%), and ALT elevation (2% vs. 1%), and hepatic functional abnormal (2% vs. <1%). The most common adverse drug reactions that resulted in drug discontinuation in patients treated with abiraterone acetate were ALT increased, AST increased and hypokalemia (<1% each).
The most common serious adverse reactions (≥1%) observed with abiraterone acetate compared to placebo were pneumonia (2% vs. 1%) and urinary tract infection (2% vs. 1%).
Abiraterone acetate may cause hypertension, hypokalemia and fluid retention as a pharmacodynamic consequence of its mechanism of action. In Phase 3 studies, anticipated mineralocorticoid effects were seen more commonly in patients treated with abiraterone acetate versus patients treated with placebo: hypokalemia (18% vs. 8%), hypertension (22% vs. 16%) and fluid retention (peripheral edema) (23% vs. 17%), respectively. In patients treated with abiraterone acetate versus patients treated with placebo, Grades 3 and 4 hypokalemia were observed in 6% versus 1% of patients, Grades 3 and 4 hypertension were observed in 7% versus 5%, and Grades 3 and 4 fluid retention edema were observed in 1% versus 1% of patients, respectively. A higher incidence of hypertension and hypokalemia was observed in Study 3011 (see Study Tables 1-6 below). Generally, these effects due to mineralocorticoid excess were successfully managed medically. Concomitant use of a corticosteroid reduces the incidence and severity of these adverse drug reactions (see WARNINGS AND PRECAUTIONS).
Clinical Trial Adverse Drug Reactions
Because clinical trials are conducted under very specific conditions the adverse reaction rates observed in the clinical trials may not reflect the rates observed in practice and should not be compared to the rates in the clinical trials of another drug. Adverse drug reaction information from clinical trials is useful for identifying drug-related adverse events and for approximating rates.
Placebo-controlled Phase 3 Study in Asymptomatic or Mildly Symptomatic mCRPC Patients (Study 302)
In a placebo-controlled, multicentre Phase 3 clinical study of asymptomatic or mildly symptomatic patients with mCRPC who were using a GnRH agonist or were previously treated with orchiectomy, abiraterone acetate was administered at a dose of 1 g daily in combination with low dose prednisone (10 mg daily) in the active treatment arm. Placebo plus low dose prednisone (10 mg daily) was given to control patients. The median duration of treatment with abiraterone acetate was 18.8 months and 11.3 months for placebo.
The most common all grade adverse reactions observed with abiraterone acetate compared to placebo were joint pain or discomfort (32% vs. 27%), peripheral edema (25% vs. 20%), hot flush (22% vs. 18%), diarrhea (22% vs. 18%), hypertension (22% vs. 13%), cough (17% vs. 14%), hypokalemia (17% vs. 13%), upper respiratory tract infection (13% vs. 8%), dyspepsia (11% vs. 5%), hematuria (10% vs. 6%), nasopharyngitis (11% vs. 8%), vomiting (13% vs. 11%), fatigue (39% vs. 34%), constipation (23% vs. 19%), contusion (13% vs. 9%), insomnia (14% vs. 11%), anemia (11% vs. 9%) and dyspnea (12% vs. 10%).
The most common serious adverse drug reactions observed with abiraterone acetate compared to placebo was urinary tract infection (1.5% vs. 0.6%), hypokalemia (0.4% vs. 0.2%) and hematuria (1.8% vs. 0.7).
The most common adverse reactions leading to clinical intervention with abiraterone acetate compared to placebo were AST elevation (4.2% vs. 0.6%), and ALT elevation (5.2% vs. 0.7%). Anticipated mineralocorticoid effects were seen more commonly in patients treated with abiraterone acetate versus patients treated with placebo: hypokalemia (17% vs. 13%), hypertension (22% vs. 13%) and fluid retention (peripheral edema) (25% vs. 20%), respectively. In patients treated with abiraterone acetate, Grades 3 and 4 hypokalemia and Grades 3 and 4 hypertension were observed in 2% and 4% of patients, respectively.
Table 1: Adverse Drug Reactions that Occurred in the Phase 3 Study with Asymptomatic or Mildly Symptomatic mCRPC Patients (Study 302) in ≥2% (all Grades) of Patients in the Abiraterone Acetate Group
| Abiraterone Acetate 1 g with Prednisone 10 mg Daily N=542 | Placebo with Prednisone 10 mg Daily N=540 | ||||||||||||
|---|---|---|---|---|---|---|---|---|---|---|---|---|---|
System Organ Class / MedDRA Preferred Term (PT) | All Grades (%) | Grade 3 (%) | Grade 4 (%) | All Grades (%) | Grade 3 (%) | Grade 4 (%) | |||||||
| Cardiac Disorders | |||||||||||||
| Cardiac failurea | 10 (1.9%) | 4 (0.8%) | 1 (0.2%) | 1 (0.2%) | 0 | 0 | |||||||
| Angina pectorisb | 14 (2.6%) | 2 (0.4%) | 0 | 6 (1.1%) | 2 (0.4%) | 0 | |||||||
| General Disorders and Administrative Site Conditions | |||||||||||||
| Edema peripheral | 134 (24.7%) | 2(0.4%) | 0 | 108 (20.0%) | 5 (0.9%) | 0 | |||||||
| Fatigue | 212 (39.1%) | 12 (2.2%) | 0 | 185 (34.3%) | 9 (1.7%) | 0 | |||||||
| Gastrointestinal Disorders | |||||||||||||
| Diarrhea | 117 (21.6%) | 5 (0.9%) | 0 | 96 (17.8%) | 5 (0.9%) | 0 | |||||||
| Dyspepsia | 60 (11.1%) | 0 | 0 | 27 (5.0%) | 1 (0.2%) | 0 | |||||||
| Constipation | 125 (23.1%) | 2 (0.2%) | 0 | 103 (19.1%) | 3 (0.6%) | 0 | |||||||
| Vomiting | 69 (12.7%) | 4 (0.7%) | 0 | 58 (10.7%) | 0 | 0 | |||||||
| Infections and Infestations | |||||||||||||
| Upper respiratory tract infection | 69 (12.7%) | 0 | 0 | 43 (8.0%) | 0 | 0 | |||||||
| Nasopharyngitis | 58 (10.7%) | 0 | 0 | 44 (8.1%) | 0 | 0 | |||||||
| Injury, Poisoning and Procedural Complications | |||||||||||||
| Contusion | 72 (13.3%) | 0 | 0 | 49 (9.1%) | 0 | 0 | |||||||
| Fall | 32 (5.9%) | 0 | 0 | 18 (3.3%) | 0 | 0 | |||||||
| Musculoskeletal and Connective Tissue Disorders | |||||||||||||
| Joint pain or discomfortc | 172 (31.7%) | 11 (2.0%) | 0 | 144 (26.7%) | 11 (2.0%) | 0 | |||||||
| Metabolism and Nutrition Disorders | |||||||||||||
| Hypokalemia | 91 (16.8%) | 12 (2.2%) | 1 (0.2%) | 68 (12.6%) | 10 (1.9%) | 0 | |||||||
| Skin and Subcutaneous Tissue Disorders | |||||||||||||
| Rash | 44 (8.1%) | 0 | 0 | 20 (3.7%) | 0 | 0 | |||||||
| Skin lesion | 19 (3.5%) | 0 | 0 | 5 (0.9%) | 0 | 0 | |||||||
| Psychiatric Disorders | |||||||||||||
| Insomnia | 73 (13.5%) | 1 (0.2%) | 0 | 61 (11.3%) | 0 | 0 | |||||||
| Respiratory, Thoracic and Mediastinal Disorders | |||||||||||||
| Cough | 94 (17.3%) | 0 | 0 | 73 (13.5%) | 1 (0.2%) | 0 | |||||||
| Dyspnea | 64 (11.8%) | 11 (2.0%) | 2 (0.4%) | 52 (9.6%) | 4 (0.7%) | 1 (0.2%) | |||||||
| Abiraterone Acetate 1 g with Prednisone 10 mg Daily N=542 | Placebo with Prednisone 10 mg Daily N=540 |
|---|
System Organ Class / MedDRA Preferred Term (PT) | All Grades (%) | Grade 3 (%) | Grade 4 (%) | All Grades (%) | Grade 3 (%) | Grade 4 (%) |
|---|---|---|---|---|---|---|
| Renal and Urinary Disorders | ||||||
| Hematuria | 56 (10.3%) | 7 (1.3%) | 0 | 30 (5.6%) | 3 (0.6%) | 0 |
| Vascular Disorders | ||||||
| Hot flush | 121 (22.3%) | 1 (0.2%) | 0 | 98 (18.1%) | 0 | 0 |
| Hypertension | 117 (21.6%) | 21 (3.9%) | 0 | 71 (13.1%) | 16 (3.0%) | 0 |
| Hematoma | 19 (3.5%) | 0 | 0 | 6 (1.1%) | 0 | 0 |
a Cardiac failure also included cardiac failure congestive, ejection fraction decreased, and left ventricular dysfunction.
b Angina pectoris included due to its clinical relevance.
c Joint pain or discomfort included: arthralgia, arthritis, bursitis, joint swelling, joint stiffness, joint range of motion decreased, joint effusion, osteoarthritis, spinal osteoarthritis, tendonitis, rheumatoid arthritis
Placebo-controlled Phase 3 Study in mCRPC Patients with Prior Treatment with Docetaxel (Study 301)
In a placebo-controlled, multicentre Phase 3 clinical study of patients with mCRPC who were using a gonadotropin releasing hormone (GnRH) agonist or were previously treated with orchiectomy, and previously treated with docetaxel, abiraterone acetate was administered at a dose of 1 g daily in combination with low dose prednisone (10 mg daily) in the active treatment arm; placebo plus low dose prednisone (10 mg daily) was given to control patients. Patients enrolled were intolerant to or had failed up to two prior chemotherapy regimens, one of which contained docetaxel. The average duration of treatment with abiraterone acetate was 32 weeks and the duration of treatment for placebo was 16 weeks.
The most common all grade adverse reactions observed with abiraterone acetate compared to placebo were myopathy (36.3% vs. 30.9%), joint pain or discomfort (30.7% vs. 24.1%), peripheral edema (24.9% vs. 17.3%), hot flush (19.0% vs. 16.8%), diarrhea (17.6% vs. 13.5%), hypokalemia (17.1% vs. 8.4%), urinary tract infection (11.5% vs. 7.1%), and cough 10.6% vs. 7.6%).
The most common serious adverse reactions observed with abiraterone acetate compared to placebo were urinary tract infection (1.8% vs. 0.8%), bone fracture (1.6% vs. 0.6%), and hypokalemia (0.8% vs. 0%).
The most common adverse reactions leading to clinical intervention with abiraterone acetate compared to placebo were AST elevation (1.4% vs. 0.5%), ALT elevation (1.1% vs. 0%), hypokalemia (1.1% vs. 0.5%), urinary tract infection (0.9% vs. 0.3%), hypertension (0.9% vs. 0.3%), congestive heart failure (0.5% vs. 0%), and angina pectoris (0.3% vs. 0%).
Anticipated mineralocorticoid effects were seen more commonly in patients treated with abiraterone acetate versus patients treated with placebo: hypokalemia (17% vs. 8%), hypertension (9% vs. 7%) and fluid retention (peripheral edema) (25% vs. 17%), respectively. In patients treated with abiraterone acetate, Grades 3 and 4 hypokalemia and Grades 3 and 4 hypertension were observed in 4% and 1% of patients, respectively.
Table 2: Adverse Drug Reactions that Occurred in a Phase 3 Study with mCRPC Patients with Prior Treatment with Docetaxel (Study 301) in ≥2% (all Grades) of Patients in the Abiraterone Acetate Group
| Abiraterone Acetate 1 g with Prednisone 10 mg Daily N=791 | Placebo with Prednisone 10 mg Daily N=394 | |||||||||||||||
|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|
System Organ Class / MedDRA Preferred Term (PT) | All Grades (%) | Grade 3 (%) | Grade 4 (%) | All Grades (%) | Grade 3 (%) | Grade 4 (%) | ||||||||||
| Cardiac Disorders | ||||||||||||||||
| Arrhythmiaa | 56 (7.0%) | 7 (0.9%) | 2 (0.2%) | 15 (4.0%) | 2 (0.5%) | 1 (0.3%) | ||||||||||
| Cardiac failureb | 16 (2.0%) | 12 (1.5%) | 1 (0.1%) | 4 (1.0%) | 0 | 1 (0.3%) | ||||||||||
| Angina pectorisc | 10 (1.3%) | 2 (0.3%) | 0 | 2 (0.5%) | 0 | 0 | ||||||||||
| General Disorders and Administrative Site Conditions | ||||||||||||||||
| Edema peripheral | 197 (24.9%) | 11 (1.4%) | 1 (0.1%) | 68 (17.3%) | 3 (0.8%) | 0 | ||||||||||
| Gastrointestinal Disorders | ||||||||||||||||
| Diarrhea | 139 (17.6%) | 5 (0.6%) | 0 | 53 (13.5%) | 5 (1.3%) | 0 | ||||||||||
| Dyspepsia | 48 (6.1%) | 0 | 0 | 13 (3.3%) | 0 | 0 | ||||||||||
| Injury, Poisoning and Procedural Complications | ||||||||||||||||
| Fracturesd | 47 (5.9%) | 8 (1.0%) | 3 (0.4%) | 9 (2.3%) | 0 | 0 | ||||||||||
| Infections and Infestations | ||||||||||||||||
| Urinary tract infection | 91 (11.5%) | 17 (2.1%) | 0 | 28 (7.1%) | 2 (0.5%) | 0 | ||||||||||
| Upper respiratory tract infection | 43 (5.4%) | 0 | 0 | 10 (2.5%) | 0 | 0 | ||||||||||
| Musculoskeletal and Connective Tissue Disorders | ||||||||||||||||
| Joint pain or discomforte | 243 (30.7%) | 37 (4.7%) | 0 | 95 (24.1%) | 17 (4.3%) | 0 | ||||||||||
| Myopathyf | 287 (36.3%) | 43 (5.4%) | 2 (0.2%) | 122 (30.9%) | 14 (4.6%) | 1 (0.3%) | ||||||||||
| Metabolism and Nutrition Disorders | ||||||||||||||||
| Hypokalemia | 135 (17.1%) | 27 (3.4%) | 3 (0.4%) | 33 (8.4%) | 3 (0.8%) | 0 | ||||||||||
| Respiratory, Thoracic and Mediastinal Disorders | ||||||||||||||||
| Cough | 84 (10.6%) | 0 | 0 | 30 (7.6%) | 0 | 0 | ||||||||||
| Renal and Urinary Disorders | ||||||||||||||||
| Urinary frequency | 57 (7.2%) | 2 (0.3%) | 0 | 20 (5.1%) | 1 (0.3%) | 0 | ||||||||||
| Nocturia | 49 (6.2%) | 0 | 0 | 16 (4.1%) | 0 | 0 | ||||||||||
| Vascular Disorders | ||||||||||||||||
| Hot flush | 150 (19.0%) | 2 (0.3%) | 0 | 66 (16.8%) | 1 (0.3%) | 0 | ||||||||||
| Hypertension | 67 (8.5%) | 10 (1.3%) | 0 | 27 (6.9%) | 1 (0.3%) | 0 | ||||||||||
a Arrhythmia included: tachycardia, atrial fibrillation, arrhythmia, bradycardia, supraventricular tachycardia, atrial tachycardia, atrioventricular block complete, conduction disorder, ventricular tachycardia, atrial flutter, bradyarrhythmia.
b Cardiac failure also included cardiac failure congestive, ejection fraction decreased, and left ventricular dysfunction.
c Angina pectoris included due to its clinical relevance.
d Fractures included all fractures with the exception of pathological fracture.
e Joint pain or discomfort included: arthralgia, arthritis, arthropathy, bursitis, joint swelling, joint stiffness, joint range of motion decreased, joint effusion, joint ankylosis, osteoarthritis, rheumatoid arthritis, spinal osteoarthritis, spondylolisthesis, tendonitis. f Myopathy included: musculoskeletal pain, musculoskeletal stiffness, musculoskeletal chest pain, myalgia, muscular weakness, musculoskeletal discomfort, myopathy, limb discomfort, blood creatine phosphokinase increased, muscle atrophy, muscle fatigue, muscle twitching, myopathy steroid.
Placebo-controlled Phase 3 Study in Patients with Newly Diagnosed High-Risk Metastatic Prostate Cancer (Study 3011 - LATITUDE)
In a Phase 3 study of patients with newly diagnosed high-risk metastatic hormone-sensitive prostate cancer who may have received up to 3 months of prior ADT, abiraterone acetate was administered at a dose of 1 g daily in combination with low-dose prednisone (5 mg daily) and ADT (a GnRH agonist or orchiectomy) in the active treatment arm; ADT and placebo were given to control patients. The median duration of treatment was 26 months with abiraterone acetate and 14 months with placebo. For patients who had crossed over from the placebo arm to abiraterone acetate, the median total treatment duration on abiraterone acetate was 12 months.
The results from the final analysis of safety were consistent with those presented in the first interim analysis. With an additional 22 months of data collection since the time of the first interim analysis, there were no clinically relevant changes in the safety profile of abiraterone acetate profile.
The most common all grade adverse reactions observed with abiraterone acetate compared to placebo were hypertension (38.4% versus 22.1%), hypokalemia (24.0% versus 3.8%), and hot flushes (15.4% versus 12.6%).
The most common serious adverse reactions observed with abiraterone acetate compared to placebo were pneumonia (2.0% versus 0.3%), urinary tract infection (1.3% versus 0.8%), and hematuria (1.3% versus 0.5%).
The most common adverse reactions leading to clinical intervention with abiraterone acetate compared to placebo were hypokalemia (9.5% versus 0.8%), hypertension (7.2% versus 2.7%), AST increased (5.7% versus 1.7%), and ALT increased (5.5% versus 1.8%).
Anticipated mineralocorticoid effects were seen more commonly in study 3011 in patients treated with abiraterone acetate versus patients treated with placebo: hypertension (40.7% versus 23.9%), hypokalemia (24.0% versus 3.8%) and fluid retention/edema (13.6% versus 11.8%). In patients treated with abiraterone acetate, Grade 3 and 4 hypokalemia was reported in 10.9% and 0.8% patients respectively. Grade 3 and 4 hypertension was 21.8% and 0.2% respectively.
Table 3: Adverse Drug Reactions that Occurred in the Phase 3 Study of Newly Diagnosed High-Risk Metastatic Hormone-sensitive Prostate Cancer Patients (Study 3011) with ≥2% increase in frequency (all Grades) in the abiraterone acetate Group compared to Placebo.
Abiraterone Acetate 1 g with Prednisone 5 mg and ADTa Daily N=597b | Placebo and ADTa Daily N=602b | ||||||||||||||
System Organ Class / MedDRA Preferred Term (PT) | All Grades (%) | Grade 3 (%) | Grade 4 (%) | All Grades (%) | Grade 3 (%) | Grade 4 (%) | |||||||||
| Cardiac Disorders | |||||||||||||||
| Cardiac Failure | 9 (1.5%) | 2 (0.3%) | 1 (0.2%) | 2 (0.3%) | 0 | 0 | |||||||||
| Angina pectoris | 10 (1.7%) | 3 (0.5%) | 1 (0.2%) | 5 (0.8%) | 0 | 0 | |||||||||
| Atrial fibrillation | 10 (1.7%) | 2 (0.3%) | 0 | 2 (0.3%) | 1 (0.2%) | 0 | |||||||||
| Infections and Infestations | ||||||
| Urinary tract infection | 44 (7.4%) | 6 (1%) | 0 | 23 (3.8%) | 5 (0.8%) | 0 |
| Upper respiratory tract infection | 42 (7.0%) | 1 (0.2%) | 0 | 29 (4.8%) | 1 (0.2%) | 0 |
| Influenza | 42 (7.0%) | 0 | 0 | 20 (3.3%) | 0 | 0 |
| Bronchitis | 24 (4.0%) | 2 (0.3%) | 0 | 8 (1.3%) | 0 | 0 |
| Injury, Poisoning and Procedural Complications | ||||||
| Rib fracture | 15 (2.5%) | 0 | 0 | 2 (0.3%) | 0 | 0 |
| Metabolism and Nutrition Disorders | ||||||
| Hypokalemia† | 143 (24.0%) | 65 (10.9%) | 5 (0.8%) | 23 (3.8%) | 9 (1.5%) | 1 (0.2%) |
| Nervous System Disorders | ||||||
| Headache | 46 (7.7%) | 2 (0.3%) | 0 | 31 (5.1%) | 1 (0.2%) | 0 |
| Psychiatric Disorders | ||||||
| Depression | 17 (2.8%) | 0 | 0 | 5 (0.8%) | 0 | 0 |
| Respiratory, Thoracic and Mediastinal Disorders | ||||||
| Cough | 41 (6.9%) | 0 | 0 | 18 (3.0%) | 0 | 0 |
| Vascular Disorders | ||||||
| Hypertension | 229 (38.4%) | 125 (20.9%) | 0 | 133 (22.1%) | 59 (9.8%) | 1 (0.2%) |
| Hot flush | 92 (15.4%) | 0 | 0 | 76 (12.6%) | 1 (0.2%) | 0 |
a All patients were receiving a GnRH agonist or had undergone orchiectomy.
b n=patients assessed for safety.
†investigator assessed AE based on reported symptoms
Cardiovascular Effects: The Phase 3 studies excluded patients with uncontrolled hypertension, clinically significant heart disease as evidenced by myocardial infarction, arterial thrombotic events in the past 6 months, severe or unstable angina, or LVEF <50% or New York Heart Association (NYHA) Class III or IV heart disease (Study 301), or NYHA Class II to IV heart disease (Studies 302 and 3011). All patients enrolled (both active and placebo-treated patients) were concomitantly treated with androgen deprivation therapy (ADT), predominantly with the use of GnRH agonists, which has been associated with diabetes, myocardial infarction, cerebrovascular accident and sudden cardiac death.
In combined data from Phase 3 trials, the incidence of cardiovascular adverse reactions in patients taking abiraterone acetate versus patients taking placebo were as follows: atrial fibrillation, 2.6% vs. 2.0%; tachycardia, 1.9% vs. 1.0%; angina pectoris, 1.7% vs. 0.8%; cardiac failure, 0.7% vs. 0.2%; and arrhythmia, 0.7% vs. 0.5%.
Hepatotoxicity: Drug-associated hepatotoxicity with elevated serum transaminases (ALT and AST) and total bilirubin has been reported in patients treated with abiraterone acetate. Across Phase 3 clinical studies, hepatotoxicity Grades 3 and 4 (e.g., ALT or AST increases of >5X ULN or bilirubin increases >1.5X ULN) were reported in approximately 6% of patients who received abiraterone acetate, typically during the first 3 months after starting treatment.
In the Phase 3 clinical study in mCRPC patients with prior treatment with docetaxel (Study 301), patients whose baseline ALT or AST were elevated were more likely to experience liver function test elevations than those beginning with normal values. When elevations of either ALT or AST
>5X ULN, or elevations in bilirubin >3X ULN were observed, abiraterone acetate was withheld or discontinued. In two instances marked increases in liver function tests occurred (see WARNINGS AND PRECAUTIONS). These two patients with normal baseline hepatic function experienced ALT or AST elevations 15X to 40X ULN and bilirubin elevations 2X to 6X ULN. Upon interruption of abiraterone acetate, both patients had normalization of their liver function tests. One patient was re-treated with abiraterone acetate. Recurrence of the elevations was not observed in this patient.
In the Phase 3 clinical study of asymptomatic or mildly symptomatic mCRPC patients (Study 302), Grade 3 or 4 ALT or AST elevations were observed in 35 (6.5%) patients treated with abiraterone acetate. Aminotransferase elevations resolved in all but three patients (two with new multiple liver metastases, and one with AST elevation approximately three weeks after the last dose of abiraterone acetate).
In the Phase 3 clinical study of newly diagnosed high-risk metastatic prostate cancer (Study 3011), Grade 3 and Grade 4 hepatotoxicity was observed in 8.2% and 0.7% of patients treated with abiraterone acetate. Ten patients (1.7%) who received abiraterone acetate were discontinued because of hepatotoxicity; two had Grade 2 hepatotoxicity, six had Grade 3 hepatotoxicity, and two had Grade 4 hepatotoxicity. No patient died of hepatotoxicity in Study 3011.
In Phase 3 clinical studies, treatment discontinuations due to ALT and AST increases or abnormal hepatic function were reported in 1.1% of patients treated with abiraterone acetate and 0.6% of patients treated with placebo, respectively; no deaths were reported due to hepatotoxicity events.
In clinical trials, the risk for hepatotoxicity was mitigated by exclusion of patients with active hepatitis or baseline hepatitis or significant abnormalities of liver function tests. In the trial with mCRPC patients who had received prior treatment with docetaxel (Study 301), patients with baseline ALT and AST ≥2.5X ULN in the absence of liver metastases and >5X ULN in the presence of liver metastases were excluded. In the trial with asymptomatic or mildly symptomatic mCRPC patients (Study 302), those with liver metastases were not eligible and patients with baseline ALT and AST ≥2.5X ULN were excluded. In the trial of newly diagnosed high-risk metastatic hormone-sensitive prostate cancer (Study 3011), patients with baseline ALT and AST >2.5X ULN, bilirubin >1.5X ULN or those with active or symptomatic viral hepatitis or chronic liver disease, ascites or bleeding disorders secondary to hepatic dysfunction were excluded. Abnormal liver function tests developing in patients participating in clinical trials were managed by treatment interruption and by permitting re-treatment only after return of liver function tests to the patient’s baseline (see DOSAGE AND ADMINISTRATION). Patients with elevations of ALT or AST >20X ULN were not re-treated. The safety of re-treatment in such patients is unknown.
Less Common Clinical Trial Adverse Drug Reactions (< 2%)
General Disorders and Administrative Site Conditions: Influenza-like illness
Investigations: Blood creatinine increased, weight increased
Infections and Infestations: Lower respiratory tract infection
Metabolism and Nutrition Disorders: Hypertriglyceridemia
Endocrine Disorders: Adrenal insufficiency
Abnormal Hematologic and Clinical Chemistry Findings:
Table 4, Table 5 and Table 6 show laboratory values of interest from the placebo-controlled Phase 3 trials.
Table 4: Selected Laboratory Abnormalities in mCRPC Asymptomatic or Mildly Symptomatic Patients who Received Abiraterone Acetate (Study 302)
Abiraterone Acetate 1 g with Prednisone 10 mg Daily N=542 | Placebo with Prednisone 10 mg Daily N=540 | ||||||||
All Grades % | Grade 3/4 % | All Grades % | Grade 3/4 % | ||||||
| ALT increased | 41 | 6 | 28 | 1 | |||||
| AST increased | 36 | 3 | 27 | 1 | |||||
| Bilirubin increased | 11 | <1 | 4 | <1 | |||||
| Hypokalemia | 14 | 2 | 8 | 1 | |||||
| Hypophosphatemia | 26 | 5 | 14 | 2 | |||||
| Hypertriglyceridemia | 22 | 0 | 17 | 0 | |||||
| Hypernatremia | 30 | <1 | 24 | <1 | |||||
| Hypercalcemia | 10 | 0 | 4 | 0 | |||||
| Lymphopenia | 36 | 7 | 30 | 0 | |||||
Table 5: Selected Laboratory Abnormalities in mCRPC Patients with Prior Treatment with Docetaxel who Received Abiraterone Acetate (Study 301)
Abiraterone Acetate 1 g with Prednisone 10 mg Daily N=791 | Placebo with Prednisone 10 mg Daily N=394 | ||||||||
All Grades % | Grade 3/4 % | All Grades % | Grade 3/4 % | ||||||
| ALT increased | 11 | 1 | 10 | <1 | |||||
| AST increased | 30 | 2 | 34 | 1 | |||||
| Bilirubin increased | 6 | <1 | 3 | 0 | |||||
| Hypokalemia | 19 | 3 | 10 | <1 | |||||
| Hypercholesterolemia | 55 | <1 | 48 | <1 | |||||
| Low phosphorus | 23 | 7 | 15 | 5 | |||||
| Hypertriglyceridemia | 62 | <1 | 53 | 0 | |||||
Table 6: Selected Laboratory Abnormalities in Patients with Newly Diagnosed High-Risk Metastatic Hormone-sensitive Prostate Cancer who Received Abiraterone Acetate (Study 3011)
Abiraterone Acetate 1 g with Prednisone 5 mg Daily N=597 | Placebo N=602 | |||||||||
All Grades % | Grade 3/4 % | All Grades % | Grade 3/4 % | |||||||
| ALT increased | 45 | 6 | 45 | 1 | ||||||
| AST increased | 46 | 5 | 46 | 2 | ||||||
| Bilirubin increased | 16 | <1 | 6 | <1 | ||||||
| Hypokalemia | 30 | 10 | 7 | 1 | ||||||
| Lymphopenia | 20 | 5 | 13 | 2 | ||||||
Post-Market Adverse Drug Reactions
The following adverse reactions have been identified during post approval use of abiraterone acetate. Because these reactions are reported voluntarily from a population of uncertain size, it is not always possible to reliably estimate their frequency or establish a causal relationship to drug exposure.
Respiratory, thoracic and mediastinal disorders: allergic alveolitis
Musculoskeletal and connective tissue disorders: rhabdomyolysis, myopathy
Hepatobiliary disorders: hepatitis fulminant, acute hepatic failure with fatalities (see Serious WARNINGS AND PRECAUTIONS Box, and WARNINGS AND PRECAUTIONS, Hepatic)
Cardiac disorders: QT prolongation and Torsades de Pointes (observed in patients who developed hypokalemia or had underlying cardiovascular conditions, see WARNINGS AND PRECAUTIONS, Cardiovascular).
Endocrine and metabolism: isolated cases of hypoglycemia (see WARNINGS AND PRECAUTIONS, Endocrine and Metabolism, Hypoglycemia).
Immune system disorders-Hypersensitivity: anaphylactic reaction (severe allergic reactions that include, but are not limited to, difficulty swallowing or breathing, swollen face, lips, tongue or throat, or an itchy rash (urticaria).
DRUG INTERACTIONS
Overview
In vitro studies indicated that CYP3A4 and SULT2A1 are the major isoenzymes involved in the metabolism of abiraterone (see DETAILED PHARMACOLOGY, Non-clinical Pharmacokinetics). Abiraterone is an inhibitor of the hepatic drug-metabolizing enzymes CYP2C8 and CYP2D6 (see Drug-Drug Interactions).
Drug-Drug Interactions
Potential for other medicinal ingredients to affect APO-ABIRATERONE ACETATE FILM COATED TABLETS
CYP3A4 inducers: Based on in vitro data, the active metabolite abiraterone is a substrate of CYP3A4. In a clinical pharmacokinetic interaction study of healthy subjects pretreated with a strong CYP3A4 inducer (rifampicin, 600 mg daily for 6 days) followed by a single dose of abiraterone acetate 1000 mg, the mean plasma AUC∞ of abiraterone was decreased by 55%. Strong inducers of CYP3A4 (e.g., phenytoin, carbamazepine, rifampicin, rifabutin, phenobarbital) during treatment with APO-ABIRATERONE ACETATE FILM COATED TABLETS are to be avoided. If patients must be co-administered a strong CYP3A4 inducer, careful evaluation of clinical efficacy must be undertaken as there are no clinical data recommending an appropriate dose adjustment.
CYP3A4 inhibitors: In a clinical pharmacokinetic interaction study, healthy subjects were administered ketoconazole, a strong CYP3A4 inhibitor, 400 mg daily for 6 days. No clinically meaningful effect on the pharmacokinetics of abiraterone was demonstrated following co- administration of a single dose of abiraterone acetate, 1000 mg at day 4.
Potential for APO-ABIRATERONE ACETATE FILM COATED TABLETS to affect other drugs
CYP1A2:
In a clinical study to determine the effects of abiraterone acetate (plus prednisone) on a single dose of the CYP1A2 substrate theophylline, no increase in systemic exposure of theophylline was observed.
CYP2D6: In the same study to determine the effects of abiraterone acetate (plus prednisone) on a single dose of the CYP2D6 substrate dextromethorphan, the systemic exposure (AUC) of dextromethorphan was increased by approximately 200%. The AUC24 for dextrorphan, the active metabolite of dextromethorphan, increased by approximately 33%.
APO-ABIRATERONE ACETATE FILM COATED TABLETS is an inhibitor of the hepatic drug-metabolizing enzyme CYP2D6. Caution is advised when APO-ABIRATERONE ACETATE FILM COATED TABLETS is administered with drugs activated by or metabolized by CYP2D6, particularly with drugs that have a narrow therapeutic index. Dose reduction of narrow therapeutic index drugs metabolized by CYP2D6 should be considered.
CYP2C8: In a CYP2C8 drug-drug interaction trial in healthy subjects, the AUC of pioglitazone was increased by 46% and the AUCs for M-III and M-IV, the active metabolites of the CYP2C8 substrate pioglitazone, each decreased by 10%, when a single dose of pioglitazone was given together with a single dose of 1000 mg abiraterone acetate. Patients should be monitored for signs of toxicity related to a CYP2C8 substrate with a narrow therapeutic index if used concomitantly with APO-ABIRATERONE ACETATE FILM COATED TABLETS. Examples of medicinal products metabolized by CYP2C8 include pioglitazone and repaglinide (see WARNINGS AND PRECAUTIONS).
CYP2C9, CYP2C19 and CYP3A4/5: In vitro studies with human hepatic microsomes demonstrated that abiraterone was a moderate inhibitor of CYP2C9, CYP2C19 and CYP3A4/5. No clinical DDI studies have been performed to confirm these in vitro findings (see DETAILED PHARMACOLOGY, Non-clinical Pharmacokinetics).
OATP1B1: In vitro, abiraterone and its major metabolites were shown to inhibit the hepatic uptake transporter OATP1B1 and as a consequence it may increase the concentrations of drugs that are eliminated by OATP1B1. There are no clinical data available to confirm transporter-based interaction.
Drug-Food Interactions
Administration of APO-ABIRATERONE ACETATE FILM COATED TABLETS with food significantly increases the absorption of abiraterone acetate. The efficacy and safety of abiraterone acetate given with food has not been established. APO-ABIRATERONE ACETATE FILM COATED TABLETS must not be taken with solid or liquid food (see DOSAGE AND ADMINISTRATION and ACTION AND CLINICAL PHARMACOLOGY,
Pharmacokinetics).
Drug-Herb Interactions
Co-administration of APO-ABIRATERONE ACETATE FILM COATED TABLETS with St. John’s wort (Hypericum perforatum) may potentially reduce the plasma concentrations of APO-ABIRATERONE ACETATE FILM COATED TABLETS. Concomitant use with St. John’s wort or products containing St. John’s wort is to be avoided.
Drug-Lifestyle Interactions
No studies on the effects of abiraterone acetate on the ability to drive or use machines have been performed. It is not anticipated that APO-ABIRATERONE ACETATE FILM COATED TABLETS will affect the ability to drive and use machines.
DOSAGE AND ADMINISTRATION
Recommended Dose
The recommended dosage of APO-ABIRATERONE ACETATE FILM COATED TABLETS is 1 g (two 500 mg tablets) as a single daily dose that must be taken on an empty stomach. No solid or liquid food should be consumed for at least two hours before the dose of APO-ABIRATERONE ACETATE FILM COATED TABLETS is taken and for at least one hour after the dose of APO-ABIRATERONE ACETATE FILM COATED TABLETS is taken. The tablets should be swallowed whole with water.
Recommended Dose of Prednisone
For metastatic castration-resistant prostate cancer (mCRPC), APO-ABIRATERONE ACETATE FILM COATED TABLETS is used with 10 mg prednisone daily. For newly diagnosed high-risk metastatic prostate cancer, APO-ABIRATERONE ACETATE FILM COATED TABLETS is used with 5 mg prednisone daily.
Administration
Patients started on APO-ABIRATERONE ACETATE FILM COATED TABLETS who were receiving a GnRH agonist should continue to receive a GnRH agonist.
Serum transaminases and bilirubin should be measured prior to starting treatment with APO-ABIRATERONE ACETATE FILM COATED TABLETS, every two weeks for the first three months of treatment and monthly thereafter.
Blood pressure, serum potassium and fluid retention should be monitored monthly (see WARNINGS AND PRECAUTIONS, Cardiovascular, Hypertension, Hypokalemia and Fluid Retention Due to Mineralocorticoid Excess).
Missed Dose
In the event of a missed daily dose of either APO-ABIRATERONE ACETATE FILM COATED TABLETS or prednisone, treatment should be resumed the following day with the usual daily dose.
Dose Adjustment in Patients with Hepatic Impairment
APO-ABIRATERONE ACETATE FILM COATED TABLETS should not be used in patients with pre-existing moderate or severe hepatic impairment (see ACTION AND CLINICAL PHARMACOLOGY).
No dosage adjustment is necessary for patients with pre-existing mild hepatic impairment.
For patients who develop hepatotoxicity during treatment with APO-ABIRATERONE ACETATE FILM COATED TABLETS (serum transaminases, ALT or AST rise above 5 times the upper limit of normal or bilirubin rises above 3 times the upper limit of normal) treatment should be withheld immediately until liver function tests normalize (see WARNINGS AND PRECAUTIONS, Hepatic).
Re-treatment following return of liver function tests to the patient’s baseline may be given at a reduced dose of 500 mg (one 500 mg tablet or two 250 mg tablets) once daily. For patients being re-treated, serum transaminases and bilirubin should be monitored at a minimum of every two weeks for three months and monthly thereafter. If hepatotoxicity recurs at the reduced dose of 500 mg daily, discontinue treatment with APO-ABIRATERONE ACETATE FILM COATED TABLETS. Reduced doses should not be taken with food (see DOSAGE AND ADMINISTRATION, Recommended Dose and Dosage Adjustment).
If patients develop severe hepatotoxicity (ALT 20 times the upper limit of normal) anytime while on therapy, APO-ABIRATERONE ACETATE FILM COATED TABLETS should be discontinued and patients should not be re-treated with APO-ABIRATERONE ACETATE FILM COATED TABLETS.
Permanently discontinue APO-ABIRATERONE ACETATE FILM COATED TABLETS for patients who develop a concurrent elevation of ALT greater than 3 times the upper limit of normal and total bilirubin greater than 2 times the upper limit of normal in the absence of biliary obstruction or other causes responsible for the concurrent elevation.
Dose Adjustment in Patients with Renal Impairment
No dosage adjustment is necessary for patients with renal impairment.
OVERDOSAGE
Human experience of overdose with abiraterone acetate is limited.
There is no specific antidote. In the event of an overdose, administration of APO-ABIRATERONE ACETATE FILM COATED TABLETS should be stopped and general supportive measures undertaken, including monitoring for arrhythmias. Liver function also should be assessed.
| For management of a suspected drug overdose, contact your regional Poison Control Centre. |
ACTION AND CLINICAL PHARMACOLOGY
Mechanism of Action
Abiraterone acetate is converted in vivo to abiraterone, an androgen biosynthesis inhibitor. Specifically, abiraterone selectively inhibits the enzyme 17α-hydroxylase/C17,20-lyase (CYP17). This enzyme is expressed in and is required for androgen biosynthesis in testicular, adrenal and prostatic tumor tissues. It catalyzes the conversion of pregnenolone and progesterone into testosterone precursors, DHEA and androstenedione, respectively, by 17-α hydroxylation and cleavage of the C17,20 bond. CYP17 inhibition also results in increased mineralocorticoid production by the adrenals (see WARNINGS AND PRECAUTIONS, Hypertension, Hypokalemia and Fluid Retention Due to Mineralocorticoid Excess).
Androgen-sensitive prostatic carcinoma responds to treatment that decreases androgen levels. Androgen deprivation therapies, such as treatment with GnRH agonists or orchiectomy, decrease androgen production in the testes but do not affect androgen production by the adrenals or in the tumor. Abiraterone acetate decreases serum testosterone and other androgens in patients to levels lower than those achieved by the use of GnRH agonists alone or by orchiectomy. Commercial testosterone assays have inadequate sensitivity to detect the effect of abiraterone acetate on serum testosterone levels, therefore, it is not necessary to monitor the effect of APO-ABIRATERONE ACETATE FILM COATED TABLETS on serum testosterone levels.
Changes in serum prostate specific antigen (PSA) levels may be observed but have not been shown to correlate with clinical benefit in individual patients.
Pharmacodynamics
Cardiac Electrophysiology: A multicentre, open-label, uncontrolled, single arm ECG assessment study was performed in 33 patients with metastatic castration-resistant prostate cancer who were medically (N=28) or surgically castrated (N=5). Patients had serial ECG recordings at baseline and on day 1 of the first and second 28-day cycles of treatment with abiraterone acetate 1g/day plus prednisone 5 mg twice daily. At steady-state on day 1 of cycle 2, the QTc interval was significantly shortened at most time points, with a maximum decrease from baseline of mean -10.7 (90% CI -14.8, -6.5) ms at 24 h post-dosing.
Androgen deprivation is associated with QTc prolongation. In this study the QTc interval averaged 435 to 440 ms at baseline and 57.6% of subjects had baseline QTc values > 450 ms prior to initiation of abiraterone acetate. Because the subjects in this trial were already androgen- deprived, the results of this study cannot be extrapolated to non-castrated populations.
Mineralocorticoid receptor antagonists: Patients in the pivotal clinical trials (COU-AA-302 and COU-AA-301) were not allowed to use the mineralocorticoid receptor antagonist spironolactone with abiraterone acetate since spironolactone has the ability to bind and activate the wild type androgen receptor, which could stimulate disease progression. The use of spironolactone with APO-ABIRATERONE ACETATE FILM COATED TABLETS should be avoided.
Prior use of ketoconazole: Based on experience in an early abiraterone acetate trial, lower rates of response might be expected in patients previously treated with ketoconazole for prostate cancer.
Pharmacokinetics
Following administration of abiraterone acetate, the pharmacokinetics of abiraterone and abiraterone acetate have been studied in healthy subjects, patients with metastatic prostate cancer and subjects without cancer with hepatic or renal impairment. Abiraterone acetate is rapidly converted in vivo to abiraterone, an androgen biosynthesis inhibitor. In clinical studies, abiraterone acetate plasma concentrations were below detectable levels (< 0.2 ng/mL) in > 99% of the analyzed samples.
Absorption: The AUC and Cmax values in patients with castration-resistant prostate cancer were 979 ng•h/mL and 216.5 ng/mL respectively. In addition, there was large inter-patient variability observed for healthy subjects and patients with castration-resistant prostate cancer.
There was an observed reduction in the clearance of patients with castration-resistant prostate cancer (33%) compared to healthy subjects. This reduction could translate to a 40% mean increase of mean population predicted exposure in patients relative to healthy subjects, but this increase may be confounded with effects of concomitant medications and food intake conditions. This difference is not considered to be clinically relevant.
Following oral administration of abiraterone acetate in the fasting state, the time to reach maximum plasma abiraterone concentration is approximately 2 hours in patients with castration-resistant prostate cancer.
Systemic exposure of abiraterone is increased when abiraterone acetate is administered with food. Abiraterone Cmax and AUC were approximately 7- and 5-fold higher, respectively, when abiraterone acetate was administered with a low-fat meal (7% fat, 300 calories) and approximately 17- and 10-fold higher, respectively when abiraterone acetate was administered with a high-fat meal (57% fat, 825 calories).
Given the normal variation in the content and composition of meals, taking APO-ABIRATERONE ACETATE FILM COATED TABLETS with meals has the potential to result in highly variable exposures. Therefore, APO-ABIRATERONE ACETATE FILM COATED TABLETS must be taken on an empty stomach. No solid or liquid food should be consumed at least two hours before taking APO-ABIRATERONE ACETATE FILM COATED TABLETS and for at least one hour after taking APO-ABIRATERONE ACETATE FILM COATED TABLETS. The tablets should be swallowed whole with water (see DOSAGE AND ADMINISTRATION).
Distribution: The plasma protein binding of 14C-abiraterone in human plasma is 99.8%. The apparent volume of distribution is approximately 5630 L, suggesting that abiraterone extensively distributes to peripheral tissues. In vitro studies show that at clinically relevant concentrations, abiraterone acetate and abiraterone are not substrates of P-glycoprotein (P-gp). In vitro studies show that abiraterone acetate is an inhibitor of P-gp. No studies have been conducted with other transporter proteins.
Metabolism: Following oral administration of 14C-abiraterone acetate as capsules, abiraterone acetate is rapidly hydrolyzed to the active metabolite abiraterone. This reaction is not CYP mediated but hypothesized to occur via an unidentified esterase(s). Abiraterone then undergoes metabolism including sulphation, hydroxylation and oxidation primarily in the liver. This results in the formation of two main plasma circulating inactive metabolites, abiraterone sulphate and N-oxide abiraterone sulphate, each accounting for approximately 43% of total radioactivity. The formation of N-oxide abiraterone sulphate is predominantly catalyzed by CYP3A4 and SULT2A1 while the formation of abiraterone sulphate is catalyzed by SULT2A1.
Excretion: The mean half-life of abiraterone in plasma is approximately 15 hours based on data from healthy subjects and approximately 12 hours based on data from patients with metastatic castration-resistant prostate cancer. Following oral administration of 14C-abiraterone acetate, approximately 88% of the radioactive dose is recovered in feces and approximately 5% in urine. The major compounds present in feces are unchanged abiraterone acetate and abiraterone (approximately 55% and 22% of the administered dose, respectively).
Special Populations and Conditions
The effect of intrinsic factors such as age and body weight has been evaluated using population pharmacokinetic approaches and no statistically significant effect was evident for any of these covariates.
Pediatrics: Abiraterone acetate has not been investigated in pediatric subjects.
Gender: All clinical study information thus far is derived from male subjects.
Hepatic Insufficiency: The pharmacokinetics of abiraterone was examined in non-mCRPC subjects with pre-existing mild (N=8) or moderate (N=8) hepatic impairment (Child-Pugh class A and B, respectively) and in healthy control subjects (N=8). Systemic exposure (AUC) to abiraterone after a single oral 1 g dose increased by approximately 1.1-fold and 3.6-fold in subjects with mild and moderate pre-existing hepatic impairment, respectively. The mean half- life of abiraterone was prolonged from approximately 13 hours in healthy subjects to approximately 18 hours in subjects with mild hepatic impairment and to approximately 19 hours in subjects with moderate hepatic impairment.
No dosage adjustment is necessary for mCRPC patients with pre-existing mild hepatic impairment. APO-ABIRATERONE ACETATE FILM COATED TABLETS should not be used in patients with pre-existing moderate or severe hepatic impairment. The safety of abiraterone acetate has not been studied in mCRPC patients with moderate or severe (Child-Pugh Class B or C) hepatic impairment at baseline.
For patients who develop hepatotoxicity during treatment with APO-ABIRATERONE ACETATE FILM COATED TABLETS suspension of treatment and dosage adjustment may be required (see DOSAGE AND ADMINISTRATION and WARNINGS AND PRECAUTIONS).
Renal Insufficiency: The pharmacokinetics of abiraterone following the administration of a single oral 1 g dose of abiraterone acetate was compared in patients with end-stage renal disease on a stable hemodialysis schedule (N=8), versus matched control subjects with normal renal function (N=8). Systemic exposure to abiraterone after a single oral 1 g dose did not increase in patients with end-stage renal disease on dialysis.
Administration of APO-ABIRATERONE ACETATE FILM COATED TABLETS in patients with renal impairment including severe renal impairment does not require dose adjustment (see DOSAGE AND ADMINISTRATION).
Genetic Polymorphism: The effect of genetic differences on the pharmacokinetics of abiraterone has not been evaluated.
STORAGE AND STABILITY
Store at room temperature 15°C to 30°C.
SPECIAL HANDLING INSTRUCTIONS
Based on its mechanism of action, APO-ABIRATERONE ACETATE FILM COATED TABLETS may harm a developing fetus; therefore, women who are pregnant or women who may be pregnant should not handle APO-ABIRATERONE ACETATE FILM COATED TABLETS without protection, e.g., gloves (see section WARNINGS AND PRECAUTIONS, Special Populations).
Any unused product or waste material should be disposed of in accordance with local requirements.
DOSAGE FORMS, COMPOSITION AND PACKAGING
APO-ABIRATERONE ACETATE FILM COATED TABLETS 500 mg “(of Abiraterone Acetate, as is) film-coated tablets are purple, oval, biconvex coated tablets. Engraved “AB500” on one side, “APO” on the other side. Inactive ingredients in the tablet core are colloidal silicon dioxide, crospovidone, lactose monohydrate, magnesium stearate, microcrystalline cellulose and sodium lauryl sulfate. The tablet film-coating contains: ferric oxide red, iron oxide black, polyethylene glycol, polyvinyl alcohol, talc and titanium dioxide.
APO-ABIRATERONE ACETATE FILM COATED TABLETS 500 mg film-coated tablets are available in bottles of 60 tablets and blisters of 14 tablets.
PART II: SCIENTIFIC INFORMATION
PHARMACEUTICAL INFORMATION
Drug Substance
Proper name: Abiraterone Acetate USP
Chemical name: (3β)-17-(3-pyridinyl) androsta-5,16-dien-3-yl acetate
Molecular formula and molecular mass: C26H33NO2 and 391.55 g/mol
Structural formula:
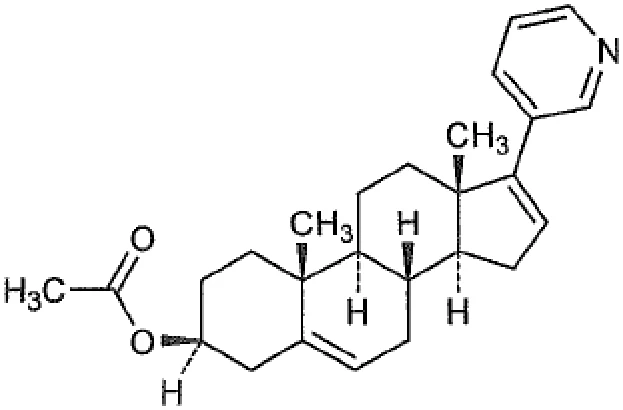
Physicochemical properties: Abiraterone acetate is a white to off-white crystalline powder. Abiraterone acetate is known to be freely soluble in dichloromethane; soluble in acetone, methanol, ethanol and isopropanol; sparingly soluble in acetonitrile and dimethyl sulfoxide; and practically insoluble in water. The melting point is between 146ºC and 148ºC. The pKa is 5.19.
CLINICAL TRIALS
Comparative Bioavailability Studies
A randomized, single-dose, double-blinded, two-treatment, four-period, fully-replicated crossover comparative bioavailability study of APO-ABIRATERONE ACETATE FILM COATED TABLETS (500 mg) of Apotex Inc. with Zytiga® 500 mg film-coated tablets of Janssen Inc. in healthy, adult subjects under fasting conditions. The results obtained from 49 subjects who completed the study are summarized as follows.
Abiraterone (1 x 500 mg abiraterone acetate) From Measured Data Geometric Mean# Arithmetic Mean (CV %) | ||||
| Parameter | Test* | Reference† | Ratio of Geometric Means (%) | 90% Confidence Interval (%) |
| AUCt (ng•h/mL) | 283.79 340.36 (66.6) | 308.08 357.24 (57.7) | 92.12 | 84.76 – 100.11 |
| AUCI (ng•h/mL) | 305.90 360.07 (63.5) | 326.39 374.84 (56.1) | 93.72 | 86.54 – 101.51 |
| Cmax (ng/mL) | 63.50 79.37 (81.7) | 60.53 74.56 (62.6) | 104.91 | 94.38 – 116.61 |
| Tmax§ (h) | 1.86 (55.4) | 1.82 (49.6) | ||
| T1/2§ (h) | 17.49 (79.7) | 15.74 (30.2) | ||
* APO-ABIRATERONE ACETATE FILM COATED TABLETS (abiraterone acetate) 500 mg film-coated tablets (Apotex Inc.) † Zytiga® (abiraterone acetate) 500 mg film-coated tablets (Janssen Inc.), was purchased in Canada. #Based on Geometric Least Squares Means. § Expressed as arithmetic means (CV %) only. | ||||
The efficacy of abiraterone acetate has been established in three randomized, placebo-controlled multicentre Phase 3 clinical studies, including two studies of patients with metastatic prostate cancer (castration-resistant prostate cancer (mCRPC) and one study of patients with newly diagnosed high-risk metastatic prostate cancer.
Placebo-controlled Phase 3 Study in Asymptomatic or Mildly Symptomatic mCRPC Patients (Study 302)
Study design and patient demographics
In this study, the efficacy of abiraterone acetate was established in patients with mCRPC (documented by positive bone scans and/or metastatic lesions on CT, MRI other than visceral metastasis) who were asymptomatic (as defined by a score of 0 to 1 on BPI-SF (Brief Pain Inventory Short Form), worst pain over the last 24 hours) or mildly symptomatic (as defined by a score of 2 to 3 on BPI- SF, worst pain over the last 24 hours) after failure of ADT, who were using a GnRH agonist during study treatment or were previously treated with orchiectomy (N=1088). Patients were randomized 1:1 to receive either abiraterone acetate or placebo. In the active treatment arm, abiraterone acetate was administered orally at a dose of 1 g daily in combination with low dose prednisone 5 mg twice daily (N=546). Control patients received placebo and low dose prednisone 5 mg twice daily (N=542).
Patients were not included in the study if they had moderate or severe pain, opiate use for severe pain, liver or visceral organ metastases, known brain metastasis, clinically significant heart disease, (as evidenced by myocardial infarction, or arterial thrombotic events in the past 6 months, severe or unstable angina, or LVEF <50% or New York Heart Association Class II to IV heart failure), prior ketoconazole for the treatment of prostate cancer, a history of adrenal gland or pituitary disorders or prostate tumor showing extensive small cell (neuroendocrine) histology. Spironolactone was a restricted concomitant therapy due to its potential to stimulate disease progression. Patients who had received prior chemotherapy or biologic therapy were excluded from the study.
The co-primary efficacy endpoints for this study were overall survival (OS) and radiographic progression free survival (rPFS). In addition to the co-primary endpoint measures, benefit was also assessed using time to opiate use for cancer pain, time to initiation of cytotoxic chemotherapy, time to deterioration in ECOG performance score by ≥ 1 point and time to PSA progression based on Prostate Cancer Working Group-2 (PCWG2) criteria. Study treatments were discontinued at the time of unequivocal clinical progression. Unequivocal clinical progression was characterized as cancer pain requiring initiation of chronic administration of opiate analgesia (oral opiate use for ≥3 weeks; parenteral opiate use for ≥7 days), or immediate need to initiate cytotoxic chemotherapy or the immediate need to have either radiation therapy or surgical intervention for complications due to tumor progression, or deterioration in ECOG performance status to Grade 3 or higher. Treatments could also be discontinued at the time of confirmed radiographic progression at the discretion of the investigator.
Radiographic progression free survival was assessed with the use of sequential imaging studies as defined by Prostate Cancer Working Group-2 (PCWG2) criteria (for bone lesions) with confirmatory bone scans and modified Response Evaluation Criteria In Solid Tumors (RECIST) criteria (for soft tissue lesions). Analysis of rPFS utilized centrally-reviewed radiographic assessment of progression.
Because changes in PSA serum concentration do not always predict clinical benefit, patients were maintained on abiraterone acetate until discontinuation criteria were met as specified for the study.
Table 7 summarizes key demographics and baseline disease characteristics. Demographics and baseline disease characteristics were balanced between the two groups.
Table 7: Key Demographics and Baseline Disease Characteristics (Phase 3 Study in Asymptomatic or Mildly Symptomatic mCRPC Patients: ITT Population)
| Abiraterone Acetate + Prednisone (N=546) | Placebo + Prednisone (N=542) | Total (N=1088) | |
| Age (years) | |||
| N | 546 | 542 | 1088 |
| Mean (SD) | 70.5 (8.80) | 70.1 (8.72) | 70.3 (8.76) |
| Median | 71.0 | 70.0 | 70.0 |
| Range | (44, 95) | (44, 90) | (44, 95) |
| Sex | |||
| n | 546 | 542 | 1088 |
| Male | 546 (100.0%) | 542 (100.0%) | 1088 (100.0%) |
| Race | |||
| n | 545 | 540 | 1085 |
| White | 520 (95.4%) | 510 (94.4%) | 1030 (94.9%) |
| 15 (2.8%) | 13 (2.4%) | 28 (2.6%) | |
| Asian | 4 (0.7%) | 9 (1.7%) | 13 (1.2%) |
| Other | 6 (1.1%) | 6 (1.1%) | 12 (1.1%) |
| Time From Initial Diagnosis to First Dose (years) | |||
| n | 542 | 540 | 1082 |
| Mean (SD) | 6.7 (4.85) | 6.5 (4.77) | 6.6 (4.81) |
| Median | 5.5 | 5.1 | 5.3 |
| Range | (0, 28) | (0, 28) | (0, 28) |
| Extent of Disease | |||
| n | 544 | 542 | 1086 |
| Bone | 452 (83.1%) | 432 (79.7%) | 884 (81.4%) |
| Bone Only | 274 (50.4%) | 267 (49.3%) | 541 (49.8%) |
| Soft Tissue or Node | 267 (49.1%) | 271 (50.0%) | 538 (49.5%) |
| ECOG Performance Status Score | |||
| n | 546 | 542 | 1088 |
| 0 | 416 (76.2%) | 414 (76.4%) | 830 (76.3%) |
| 1 | 130 (23.8%) | 128 (23.6%) | 258 (23.7%) |
| Baseline PSA (ng/mL) | |||
| n | 546 | 539 | 1085 |
| Mean (SD) | 133.38 (323.639) | 127.63 (387.878) | 130.52 (356.846) |
| Median | 42.01 | 37.74 | 39.51 |
| Range | (0.0, 3927.4) | (0.7, 6606.4) | (0.0, 6606.4) |
| Baseline Hemoglobin (g/dL) | |||
| n | 545 | 538 | 1083 |
| Mean (SD) | 12.97 (1.22) | 12.99 (1.22) | 12.98 (1.22) |
| Median | 13.0 | 13.1 | 13.1 |
| Range | (7.2,16.6) | (7.0, 15.7) | (7.0, 16.6) |
| Baseline Alkaline Phosphatase (IU/L) | |||
| n | 546 | 539 | 1085 |
| Mean (SD) | 137.4 (166.88) | 148.1 (248.11,) | 142.8 (211.15) |
| Median | 93.0 | 90.0 | 91.0 |
| Range | (32, 1927) | (21, 3056) | (21, 3056) |
| Baseline Lactate Dehydrogenase (IU/L) | |||
| n | 543 | 536 | 1079 |
| Mean (SD) | 199.9 (78.57) | 196.8 (59.20) | 198.3 (69.61) |
| Median | 187.0 | 184.0 | 185.0 |
| Range | (60, 871) | (87, 781) | (60, 871) |
Study results
A median of 15 cycles (60 weeks) were administered in the abiraterone acetate group compared with 9 cycles (36 weeks) in the placebo group. The mean duration of treatment with abiraterone acetate was 18.8 months and 11.3 months for placebo.
At the planned rPFS analysis there were 401 radiographic progression events; 150 (28%) of patients treated with abiraterone acetate and 251 (46%) of patients treated with placebo had radiographic evidence of progression or had died. A significant difference in rPFS between treatment groups was observed, see Table 8 and Figure 1. rPFS analyses by subgroup are presented in Figure 2.
Table 8: rPFS of Patients Treated with Either Abiraterone Acetate or Placebo in Combination with Prednisone Plus GnRH Agonists or Prior Orchiectomy (ITT Population)
| Abiraterone Acetate N=546 | Placebo N=542 | ||||||
| Progression or death | 150 (28%) | 251 (46%) | |||||
| Median rPFS (months) (95% CI) | Not reached (11.66, NE) | 8.3 (8.12, 8.54) | |||||
| Hazard ratio** (95% CI) | 0.425 (0.347, 0.522) | ||||||
| p-value* | <0.0001 | ||||||
NE=Not Estimated*
From a log-rank test of the equality of two survival curves over the time interval, and stratified by baseline ECOG score (0 or 1)
** Hazard Ratio is derived from a stratified proportional hazards model. Hazard ratio <1 favors abiraterone acetate
Figure 1: Kaplan Meier Curves of rPFS in Patients Treated with Either Abiraterone Acetate or Placebo in Combination with Prednisone plus GnRH Agonists or Prior Orchiectomy
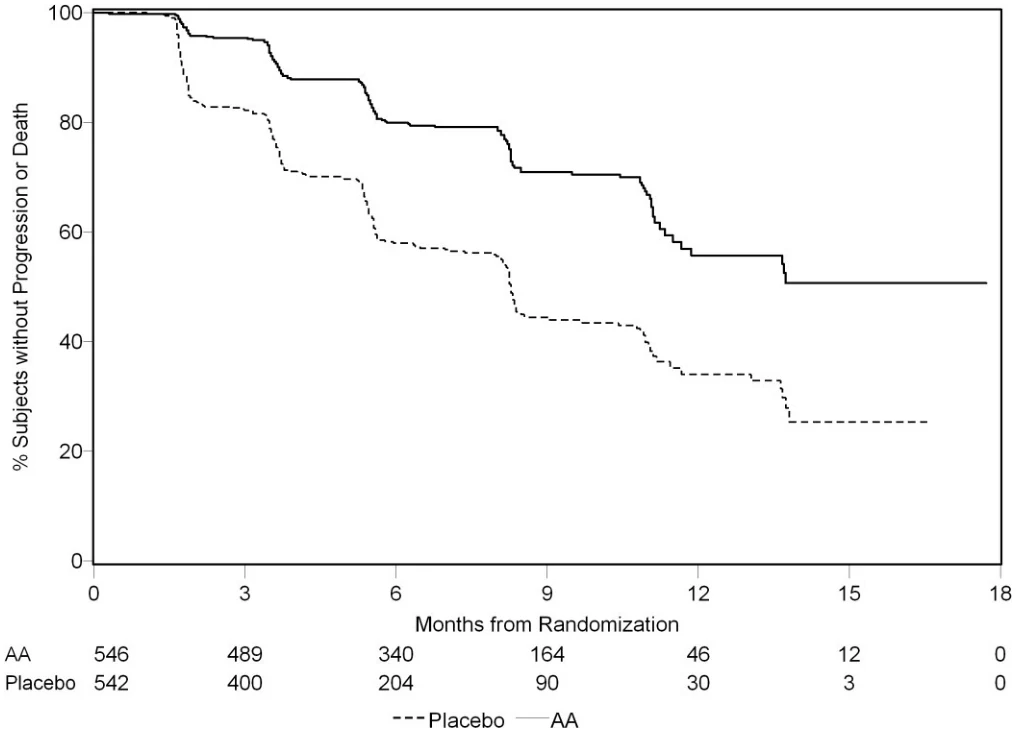
Figure 2: rPFS by Subgroup (ITT Population)
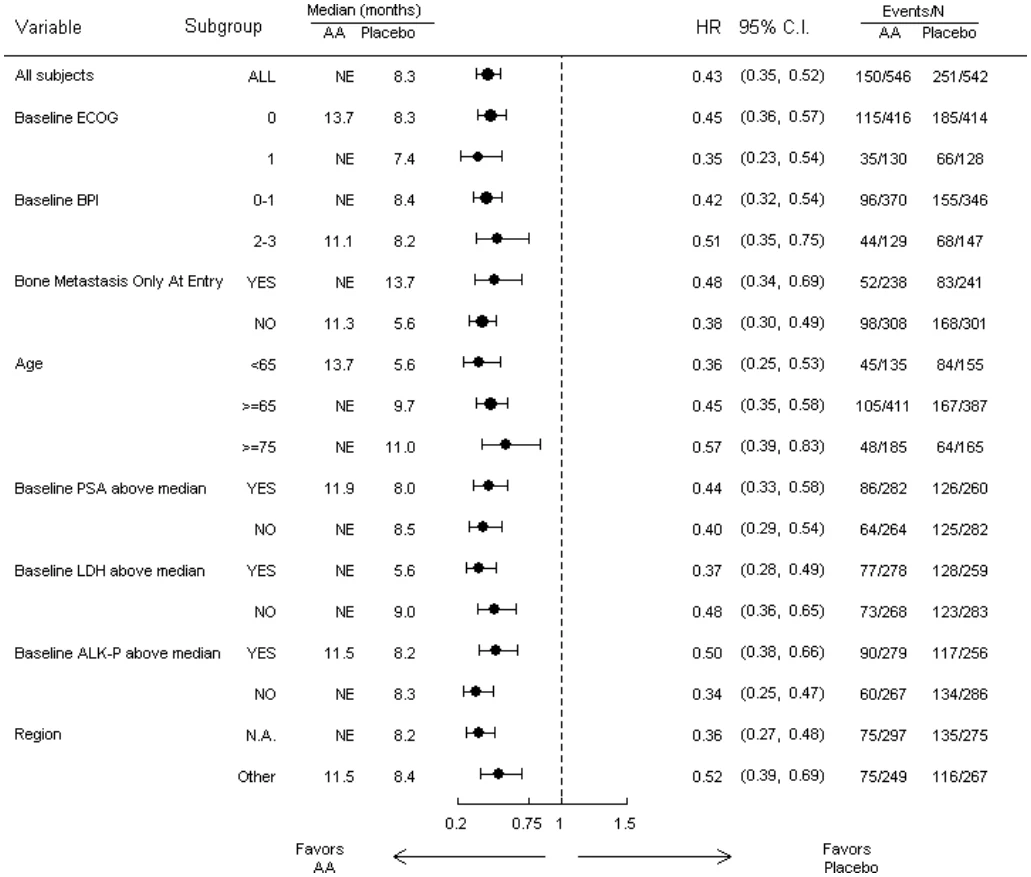
The HR within each subgroup was estimated using a nonstratified Cox proportional hazard model. AA=abiraterone acetate; ALP=alkaline phosphatase; BPI=Brief Pain Inventory; C.I.=confidence interval;
ECOG=Eastern Cooperative Oncology Group; HR=hazard ratio; LDH=lactic dehydrogenase; N.A.=North America; NE=not estimable; No.=number; PSA=prostate-specific antigen
A planned interim analysis for OS was conducted after 333 deaths were observed. At this time, the IDMC determined that equipoise no longer existed between the study arms and recommended the trial be unblinded based on the statistically and clinically significant improvements in rPFS, together with improvements in other clinically important secondary endpoints and a positive trend towards improved overall survival. As a result, patients in the placebo group were offered treatment with abiraterone acetate. Overall survival at the IA was longer for abiraterone acetate than placebo with a 25% reduction in risk of death (HR = 0.752; 95 % CI: 0.606 to 0.934, p=0.0097) but OS was not mature and the results did not meet the pre-specified value for statistical significance of 0.0008 (Table 9). Overall survival continued to be followed after this interim analysis.
The planned final analysis for OS was conducted after 741 deaths were observed (median follow-up of 49 months). Sixty five percent (354 of 546) of patients treated with abiraterone acetate, compared with 71% (387 of 542) of patients treated with placebo, had died. A statistically significant OS benefit in favor of the abiraterone acetate - treated group was demonstrated with a 19.4% reduction in risk of death (HR=0.806; 95% CI: [0.697, 0.931], p = 0.0033) and an improvement in median OS of 4.4 months (abiraterone acetate 34.7 months, placebo 30.3 months) (see Table 9 and Figure 3). Sixty seven percent of patients treated with abiraterone acetate and 80% of patients treated with placebo received subsequent therapies that had the potential to prolong OS for this patient population. Subsequent therapies included abiraterone acetate, 69 (13%) and 238 (44%); docetaxel, 311 (57%) and
331 (61%); cabazitaxel, 100 (18%) and 105 (19%); and enzalutamide 87 (16%) and 54 (10%) for patients receiving abiraterone acetate or placebo, respectively. Survival analyses by subgroup are presented in Figure 4.
Table 9: Overall Survival of Asymptomatic or mildly symptomatic mCRPC Patients Treated with Either Abiraterone Acetate or Placebo in Combination with Prednisone Plus GnRH Agonists or Prior Orchiectomy (ITT Population)
| Abiraterone Acetate N=546 | Placebo N=542 | |||||||
| Interim Analysis | ||||||||
| Deaths | 147 (27%) | 186 (34%) | ||||||
| Median OS (months) (95% CI) | Not reached (NE, NE) | 27.2 (25.95, NE) | ||||||
| Hazard ratio** (95% CI) | 0.752 (0.606, 0.934) | |||||||
| p-value* | 0.0097 | |||||||
| Final Survival Analysis | ||||||||
| Deaths | 354 (65%) | 387 (71%) | ||||||
| Median OS (months) (95% CI) | 34.7 (32.7, 36.8) | 30.3 (28.7, 33.3) | ||||||
| Hazard ratio** (95% CI) | 0.806 (0.697, 0.931) | |||||||
| p-value* | 0.0033 | |||||||
NE=Not Estimated
* From a log-rank test of the equality of two survival curves over the time interval, and stratified by baseline ECOG score (0 or 1)
** Hazard Ratio is derived from a stratified proportional hazards model. Hazard ratio <1 favors abiraterone acetate
Figure 3: Kaplan Meier Survival Curves of Patients Treated with Either Abiraterone Acetate or Placebo in Combination with Prednisone plus GnRH Agonists or Prior Orchiectomy (Final analysis; ITT Population)
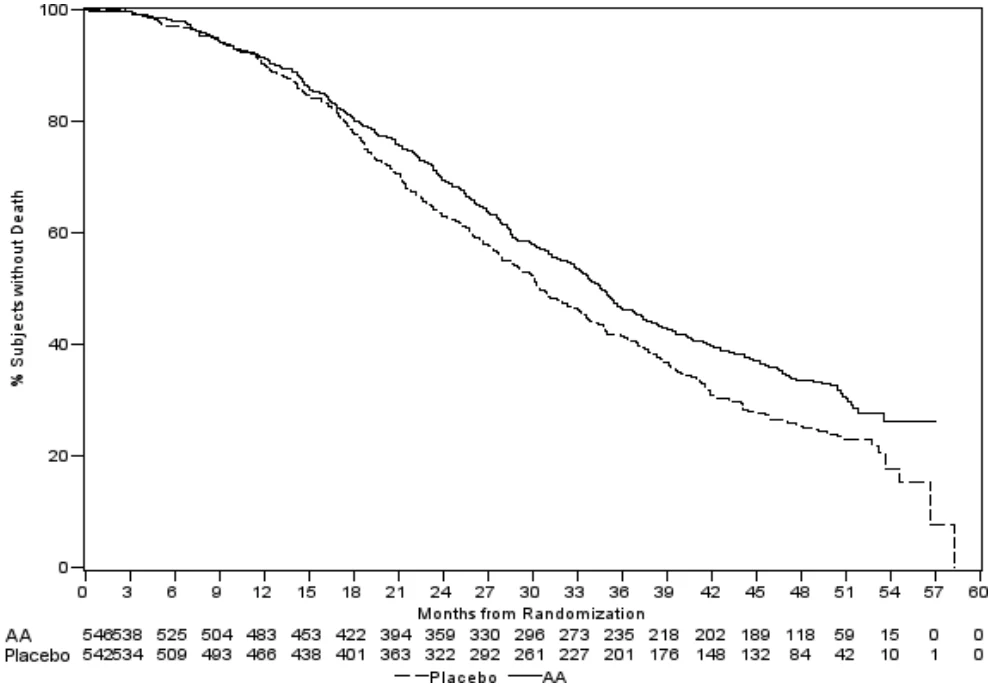
Figure 4: Overall Survival by Subgroup (Final Analysis) (ITT Population)
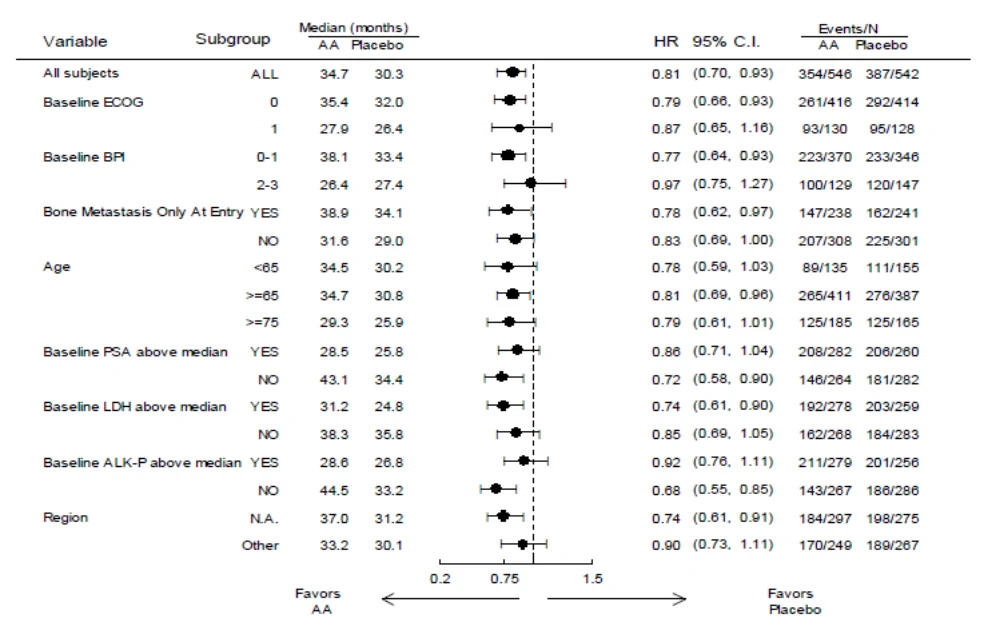
AA= Abiraterone Acetate®; ALK-P=alkaline phosphatase; BPI=Brief Pain Inventory; C.I.=confidence interval; ECOG=Eastern Cooperative Oncology Group performance score; HR=hazard ratio; LDH=lactic dehydrogenase; N.A.=North America; NE=not evaluable
Subgroup analyses showed a consistent but significant rPFS effect and a consistent trend in overall survival effect favoring treatment with abiraterone acetate.
The observed improvements in the co-primary efficacy endpoints of OS and rPFS were supported by clinical benefit favoring abiraterone acetate vs. placebo treatment in the following prospectively assessed secondary endpoints as follows:
Time to opiate use for cancer pain: The median time to opiate use for prostate cancer pain was
33.4 months for patients receiving abiraterone acetate and was 23.4 months for patients receiving placebo (HR=0.721; 95% CI: [0.614, 0.846], p=0.0001).
Time to initiation of cytotoxic chemotherapy: The median time to initiation of cytotoxic chemotherapy was 25.2 months for patients receiving abiraterone acetate and 16.8 months for patients receiving placebo (HR=0.580; 95% CI: [0.487, 0.691], p<0.0001).
Time to deterioration in ECOG performance score: The median time to deterioration in ECOG performance score by ≥ 1 point was 12.3 months for patients receiving abiraterone acetate and 10.9 months for patients receiving placebo (HR=0.821; 95% CI: [0.714, 0.943], p=0.0053).
PSA Based Endpoints: PSA-based endpoints are not validated surrogate endpoints of clinical benefit in this patient population. Nevertheless, patients receiving abiraterone acetate demonstrated a significantly higher total PSA response rate (defined as a ≥ 50% reduction from baseline), compared with patients receiving placebo: 62% versus 24%, p<0.0001. The median time to PSA progression (time interval from randomization to PSA progression, according to PSAWG criteria) was 11.1 months for patients treated with abiraterone acetate and 5.6 months for patients treated with placebo (HR=0.488; 95% CI: [0.420, 0.568], p<0.0001).
Placebo-controlled Phase 3 Study in mCRPC Patients with Prior Docetaxel Treatment (Study
301)
Study design and patient demographics
In this study, the efficacy of abiraterone acetate was established in patients with mCRPC who had received prior chemotherapy containing docetaxel. Patients continued to be treated with a GnRH agonist during study treatment or were previously treated with orchiectomy (N=1195). Patients were randomized 2:1 to receive either abiraterone acetate or placebo. In the active treatment arm, abiraterone acetate was administered orally at a dose of 1 g daily in combination with low dose prednisone 5 mg twice daily (N=797). Control patients received placebo and low dose prednisone 5 mg twice daily (N=398).
Patients were not included in the study if they had clinically significant heart disease, (as evidenced by myocardial infarction, or arterial thrombotic events in the past 6 months, severe or unstable angina, or LVEF <50% or New York Heart Association Class III or IV heart failure), prior ketoconazole for the treatment of prostate cancer, a history of adrenal gland or pituitary disorders or prostate tumor showing extensive small cell (neuroendocrine) histology.
Spironolactone was a restricted concomitant therapy due to its potential to stimulate disease progression.
The primary efficacy endpoint was OS.
PSA serum concentration independently does not always predict clinical benefit. In this study it was also recommended that patients be maintained on their study drugs until there was PSA progression (confirmed 25% increase over the patient’s baseline/nadir) together with protocol- defined radiographic progression and symptomatic or clinical progression.
Table 10 summarizes key demographics and baseline disease characteristics. Demographics and baseline disease characteristics were balanced between the two groups.
| Table 10: Key Demographics and Baseline Disease Characteristics Phase 3 Study in mCRPC patients with prior Docetaxel treatment: ITT Population | |||
| Abiraterone Acetate + Prednisone (N=797) | Placebo + Prednisone (N=398) | Total (N=1195) | |
| Age (years) | |||
| N | 797 | 397 | 1194 |
| Mean (SD) | 69.1 (8.40) | 68.9 (8.61) | 69.0 (8.46) |
| Median | 69.0 | 69.0 | 69.0 |
| Range | (42, 95) | (39, 90) | (39, 95) |
| Sex | |||
| N | 797 | 398 | 1195 |
| Male | 797 (100.0%) | 398 (100.0%) | 1195 (100.0%) |
| Race | |||
| N | 796 | 397 | 1193 |
| White | 743 (93.3%) | 368 (92.7%) | 1111 (93.1%) |
| 28 (3.5%) | 15 (3.8%) | 43 (3.6%) | |
| Asian | 11 (1.4%) | 9 (2.3%) | 20 (1.7%) |
| Other | 14 (1.8%) | 5 (1.3%) | 19 (1.6%) |
| Time since initial diagnosis to first dose(days) | |||
| N | 791 | 394 | 1185 |
| Mean (SD) | 2610.9 (1630.21) | 2510.1 (1712.36) | 2577.4 (1657.93) |
| Median | 2303.0 | 1928.0 | 2198.0 |
| Range | (175, 9129) | (61, 8996) | (61, 9129) |
| Evidence of disease progression | |||
| N | 797 | 398 | 1195 |
| PSA only | 238 (29.9%) | 125 (31.4%) | 363 (30.4%) |
| Radiographic progression with or without PSA progression | 559 (70.1%) | 273 (68.6%) | 832 (69.6%) |
| Extent of disease | |||
| Bone | 709 (89.2%) | 357 (90.4%) | 1066 (89.6%) |
| Soft tissue, not otherwise specified | 0 | 0 | 0 |
| Node | 361 (45.4%) | 164 (41.5%) | 525 (44.1%) |
| Viscera, not otherwise specified | 1 (0.1%) | 0 (0.0%) | 1 (0.1%) |
| Liver | 90 (11.3%) | 30 (7.6%) | 120 (10.1%) |
| Lungs | 103 (13.0%) | 45 (11.4%) | 148 (12.4%) |
| Prostate mass | 60 (7.5%) | 23 (5.8%) | 83 (7.0%) |
| Other viscera | 46 (5.8%) | 21 (5.3%) | 67 (5.6%) |
| Other tissue | 40 (5.0%) | 20 (5.1%) | 60 (5.0%) |
| ECOG performance status | |||
| N | 797 | 398 | 1195 |
| 0 or 1 | 715 (89.7%) | 353 (88.7%) | 1068 (89.4%) |
| 2 | 82 (10.3%) | 45 (11.3%) | 127 (10.6%) |
| Pain | |||
| N | 797 | 398 | 1195 |
| Present | 357 (44.8%) | 179 (45.0%) | 536 (44.9%) |
| Absent | 440 (55.2%) | 219 (55.0%) | 659 (55.1%) |
| Baseline PSA (ng/mL) | |||
| N | 788 | 393 | 1181 |
| Mean (SD) | 439.18 (888.476) | 400.58 (810.549) | 426.33 (863.173) |
| Median | 128.80 | 137.70 | 131.40 |
| Range | (0.4, 9253.0) | (0.6, 10114.0) | (0.4, 10114.0) |
Eleven percent of patients enrolled had an ECOG performance score of 2; 70% had radiographic evidence of disease progression with or without PSA progression; 70% had received one prior cytotoxic chemotherapy and 30% received two. As required in the protocol, 100% of patients had received docetaxel therapy prior to treatment with abiraterone acetate. All docetaxel containing regimens were considered as one line of therapy. Liver metastasis was present in 11% of patients treated with abiraterone acetate.
Study results
A median of 8 cycles (32 weeks) were administered in the abiraterone acetate group compared with 4 cycles (16 weeks) in the placebo group. The proportion of patients who required dose reductions was low; 4% in the abiraterone acetate group and 1% in the placebo group had dose reductions and 17% and 16%, respectively, required dose interruptions.
In a planned interim analysis conducted after 552 deaths were observed, 42% (333 of 797) of patients treated with abiraterone acetate, compared with 55% (219 of 398) of patients treated with placebo, had died. A statistically significant improvement in median overall survival was seen in patients treated with abiraterone acetate (see Table 11 and Figure 5).
An updated survival analysis was conducted when 775 deaths (97% of the planned number of deaths for final analysis) were observed. Results from this analysis were consistent with those from the interim analysis (Table 11).
Table 11: Overall Survival of Patients Treated with Either Abiraterone Acetate or Placebo in
Combination with Prednisone Plus GnRH Agonists or Prior Orchiectomy
| Abiraterone Acetate (N=797) | Placebo (N=398) | ||||||||
| Primary Survival Analysis | |||||||||
| Deaths (%) | 333 (42%) | 219 (55%) | |||||||
| Median survival (months) (95% CI) | 14.8 (14.1, 15.4) | 10.9 (10.2, 12.0) | |||||||
| p-value a | <0.0001 | ||||||||
| Hazard ratio (95% CI) b | 0.646 (0.543, 0.768) | ||||||||
| Updated Survival Analysis | |||||||||
| Deaths (%) | 501 (63%) | 274 (69%) | |||||||
| Median survival (months) (95% CI) | 15.8 (14.8, 17.0) | 11.2 (10.4, 13.1) | |||||||
| Hazard ratio (95% CI) b | 0.740 (0.638, 0.859) | ||||||||
a P-value is derived from a log-rank test stratified by ECOG performance status score (0–1 vs. 2), pain score (absent vs. present), number of prior chemotherapy regimens (1 vs. 2), and type of disease progression (PSA only vs. radiographic). b Hazard ratio is derived from a stratified proportional hazards model. Hazard ratio < 1 favors abiraterone acetate. | |||||||||
At all evaluation time points after the initial few months of treatment, a higher proportion of patients treated with abiraterone acetate remained alive, compared with the proportion of patients treated with placebo (see Figure 5).
Figure 5: Kaplan Meier Survival Curves of Patients Treated with either Abiraterone Acetate or Placebo in Combination with Prednisone plus GnRH Agonists or Prior Orchiectomy (planned interim analysis)
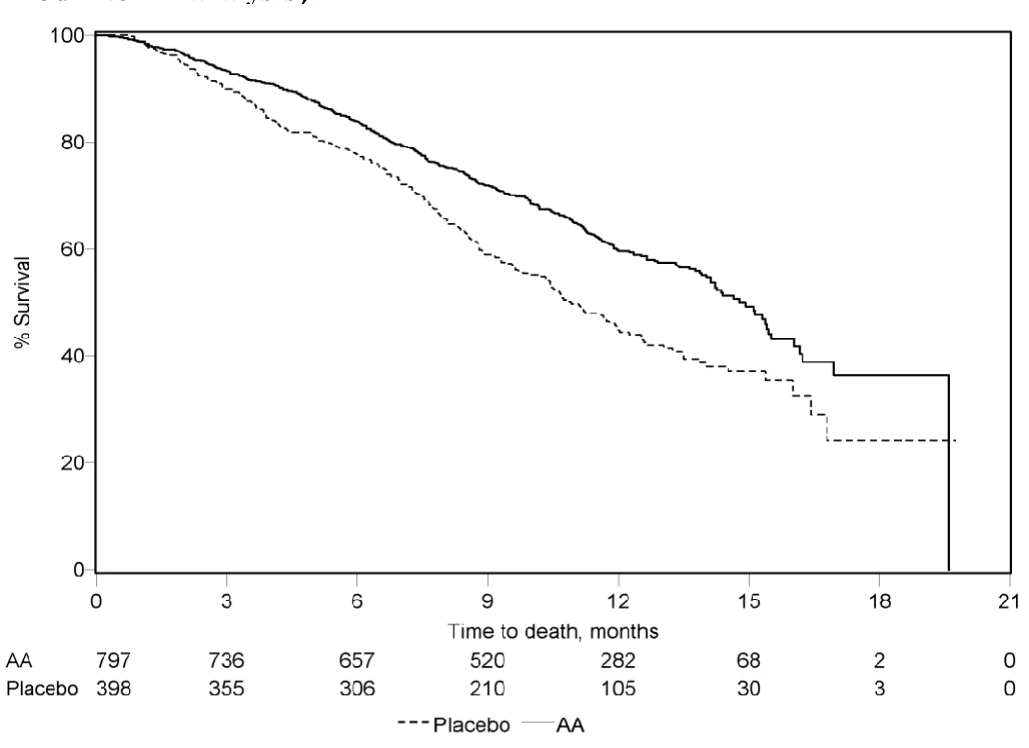
AA= abiraterone acetate Survival analyses by subgroup are presented in Figure 6.
Figure 6: Overall Survival by Subgroup
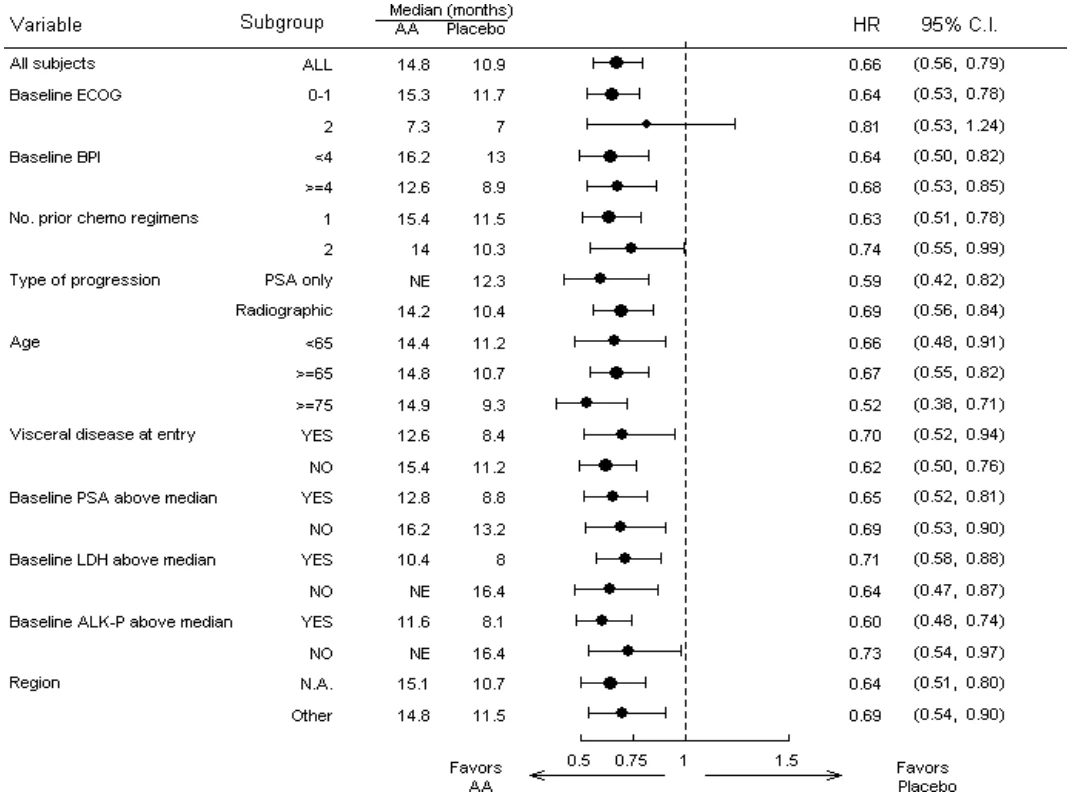
AA= Abiraterone Acetate; ALK-P=alkaline phosphatase; BPI=Brief Pain Inventory; C.I.=confidence interval; ECOG=Eastern Cooperative Oncology Group performance score; HR=hazard ratio; LDH=lactic dehydrogenase; N.A.=North America; NE=not evaluable
Subgroup analyses showed a consistent favorable survival effect for treatment with abiraterone acetate by presence of pain at baseline, 1 or 2 prior chemotherapy regimens, type of progression, baseline PSA score above median and presence of visceral disease at entry.
In addition to the observed improvement in overall survival, all secondary study endpoints favored abiraterone acetate and were statistically significant after adjusting for multiple testing. PSA- based endpoints are not validated surrogate endpoints of clinical benefit in this patient population. Nevertheless, patients receiving abiraterone acetate demonstrated a significantly higher total PSA response rate (defined as a ≥ 50% reduction from baseline), compared with patients receiving placebo: 38% versus 10%, p<0.0001. The median time to PSA progression (time interval from randomization to PSA progression, according to PSAWG criteria) was 10.2 months for patients treated with abiraterone acetate and 6.6 months for patients treated with placebo (HR=0.580; 95% CI: [0.462, 0.728], p<0.0001).
The rPFS was the time from randomization to the occurrence of either tumor progression in soft tissue according to modified RECIST criteria (with CT or MRI, until an increase above baseline of at least 20% in the longest diameter of target lesions or the appearance of new lesions), or by bone scan (≥ 2 new lesions). A confirmatory bone scan was not mandatory. The median rPFS was 5.6 months for patients treated with abiraterone acetate and 3.6 months for patients who received placebo (HR=0.673; 95% CI: [0.585, 0.776], p<0.0001).
Pain
The proportion of patients with pain palliation was statistically significantly higher in the abiraterone acetate group than in the placebo group (44% versus 27%, p=0.0002). A responder for pain palliation was defined as a patient who experienced at least a 30% reduction from baseline in the Brief Pain Inventory – Short Form (BPI-SF) worst pain intensity score over the last 24 hours without any increase in analgesic usage score observed at two consecutive evaluations four weeks apart. Only patients with a baseline pain score of ≥ 4 and at least one post-baseline pain score were analyzed (N=512) for pain palliation.
Pain progression was defined as an increase from baseline of ≥ 30% in the BPI-SF worst pain intensity score over the previous 24 hours without a decrease in analgesic usage score observed at two consecutive visits, or an increase of ≥ 30% in analgesic usage score observed at two consecutive visits. The time to pain progression at the 25th percentile was 7.4 months in the abiraterone acetate group, versus 4.7 months in the placebo group.
Skeletal-Related Events
The time to first skeletal-related event at the 25th percentile in the abiraterone acetate group was twice that of the control group at 9.9 months vs. 4.9 months. A skeletal-related event was defined as a pathological fracture, spinal cord compression, palliative radiation to bone, or surgery to bone.
Placebo-controlled Phase 3 Study in Newly Diagnosed High-Risk Metastatic Prostate Cancer Patients (Study 3011 - LATITUDE)
Study design and patient demographics
The study enrolled patients who were diagnosed with metastatic prostate cancer within 3 months of randomization and had high-risk prognostic factors. Patients could have received up to 3 months of prior ADT treatment. High-risk prognosis was defined as having at least 2 of the following 3 risk factors: (1) Gleason score of ≥8; (2) presence of 3 or more lesions on bone scan; (3) presence of measurable visceral (excluding lymph node disease) metastasis. In the active arm, abiraterone acetate was administered at a dose of 1 g daily in combination with low dose prednisone or prednisolone 5 mg once daily in addition to ADT (GnRH agonist or orchiectomy), which was the standard of care treatment. Patients in the control arm received ADT and placebos for both abiraterone acetate and prednisone. Patients with uncontrolled hypertension, significant heart disease, or NYHA Class II or worse heart failure were excluded.
Co-primary efficacy endpoints were OS and rPFS. Radiographic progression-free survival was defined as the time from randomization to the occurrence of radiographic progression or death from any cause. Radiographic progression included progression by bone scan (according to modified PCWG2) or progression of soft tissue lesions by CT or MRI (according to RECIST 1.1). Secondary endpoints included time to skeletal-related event (SRE), time to subsequent therapy for prostate cancer, time to initiation of chemotherapy, time to pain progression and time to PSA progression.
Treatment continued until disease progression, withdrawal of consent, the occurrence of unacceptable toxicity, or death.
The key demographics and baseline characteristics are shown in Table 12 below.
Table 12: Key Demographics and Baseline Disease Characteristics (Phase 3 Study in Newly Diagnosed High-Risk Metastatic Prostate Cancer Patients: ITT Population)
Abiraterone Acetate + Prednisone + ADT (N=597) | Placebo + ADT (N=602) | Total (N=1199) | |
| Age (years) | |||
| N | 597 | 602 | 1199 |
| Mean (SD) | 67.3 (8.48) | 66.8 (8.72) | 67.1 (8.60) |
| Median | 68.0 | 67.0 | 67.0 |
| Range | (38; 89) | (33; 92) | (33; 92) |
| Sex | |||
| N | 597 | 602 | 1199 |
| Male | 597 (100.0%) | 602 (100.0%) | 1199 (100.0%) |
| Race | |||
| N | 597 | 602 | 1199 |
| White | 409 (68.5%) | 423 (70.3%) | 832 (69.4%) |
| Black or African American | 15 (2.5%) | 10 (1.7%) | 25 (2.1%) |
| Asian | 125 (20.9%) | 121 (20.1%) | 246 (20.5%) |
| Other | 43 (7.2%) | 37 (6.1%) | 80 (6.7%) |
| Time from initial diagnosis to first dose (months) | |||
| N | 597 | 602 | 1199 |
| Mean (SD) | 1.8 (0.73) | 1.9 (0.75) | 1.9 (0.74) |
| Median | 1.8 | 2.0 | 1.8 |
| Range | (0; 3) | (0; 4) | (0; 4) |
| Current Extent of Disease | |||
| N | 596 | 600 | 1196 |
| Bone | 580 (97.3%) | 585 (97.5%) | 1165 (97.4%) |
| Liver | 32 (5.4%) | 30 (5.0%) | 62 (5.2%) |
| Lungs | 73 (12.2%) | 72 (12.0%) | 145 (12.1%) |
| Node | 283 (47.5%) | 287 (47.8%) | 570 (47.7%) |
| Prostate mass | 151 (25.3%) | 154 (25.7%) | 305 (25.5%) |
| Viscera | 18 (3.0%) | 13 (2.2%) | 31 (2.6%) |
| Soft tissue | 9 (1.5%) | 15 (2.5%) | 24 (2.0%) |
| Other | 2 (0.3%) | 0 | 2 (0.2%) |
| Subjects with high risk at Screening (IWRS) | 597 (100.0%) | 601 (99.8%) | 1198 (99.9%) |
| GS≥8 + ≥3 bone lesions | 573 (96.0%) | 569 (94.7%) | 1142 (95.3%) |
| GS≥8 + Measurable visceral | 82 (13.7%) | 87 (14.5%) | 169 (14.1%) |
| ≥3 bone lesions + Measurable visceral | 84 (14.1%) | 85 (14.1%) | 169 (14.1%) |
| GS≥8 + ≥3 bone lesions + Measurable visceral | 71 (11.9%) | 70 (11.6%) | 141 (11.8%) |
| Baseline Pain score (BPI-SF Item3) | |||
| N | 570 | 579 | 1149 |
| Mean (SD) | 2.2 (2.45) | 2.2 (2.40) | 2.2 (2.42) |
| ECOG performance status at baseline | |||
| N | 597 | 602 | 1199 |
| 0 | 326 (54.6%) | 331 (55.0%) | 657 (54.8%) |
| 1 | 245 (41.0%) | 255 (42.4%) | 500 (41.7%) |
| 2 | 26 (4.4%) | 16 (2.7%) | 42 (3.5%) |
| Baseline PSA (ng/mL) | |||
| N | 595 | 600 | 1195 |
| Mean (SD) | 263.24 (791.440) | 201.67 (647.807) | 232.33 (723.252) |
| Median | 25.43 | 23.05 | 23.85 |
| Range | (0.0; 8775.9) | (0.1; 8889.6) | (0.0; 8889.6) |
| Baseline Hemoglobin (g/L) | |||
| N | 597 | 602 | 1199 |
| Mean (SD) | 130.52 (16.959) | 131.57 (17.430) | 131.05 (17.198) |
| Median | 1 | 133.00 | 132.00 |
| Range | (90.0; 175.0) | (89.0; 174.0) | (89.0; 175.0) |
| Baseline Lactate Dehydrogenase (U/L) | |||
| N | 591 | 595 | 1186 |
| Mean (SD) | 199.3 (133.11) | 193.6 (104.22) | 196.4 (119.47) |
| Median | 177.0 | 176.0 | 177.0 |
| Range | (73; 2634) | (67; 1444) | (67; 2634) |
Study results
A median of 28 cycles (112 weeks) were administered in the abiraterone acetate group compared with 15 cycles (62 weeks) in the placebo group. The median total treatment duration was 26 months in the abiraterone acetate group and 14 months in the placebo group.
At the planned rPFS analysis there were 593 events; 239 (40.0%) of patients treated with abiraterone acetate and 354 (58.8%) of patients treated with placebo had radiographic evidence of progression or had died. A statistically significant difference in rPFS between treatment groups was observed (see Table 13 and Figure 7). rPFS analyses by subgroup are presented in Figure 8.
| Table 13: Radiographic Progression-Free Survival - Stratified Analysis; ITT Population (Study 3011) | ||||||||||
| Abiraterone Acetate+ Prednisone | Placebo | |||||||||
| N=597 | N=602 | |||||||||
| Event | 239 (40.0%) | 354 (58.8%) | ||||||||
| Median rPFS (95% CI) | 33.02 (29.57, NE) | 14.78 (14.69, 18.27) | ||||||||
| Hazard ratio (95% CI)b | 0.466 (0.394, 0.550) | |||||||||
| p valuea | <0.0001 | |||||||||
+=censored observation, NE=not estimable. The radiographic progression and death are considered in defining the rPFS event. a p value is from a log-rank test stratified by ECOG PS score (0/1 or 2) and visceral (absent or present). b Hazard ratio is from stratified proportional hazards model. Hazard ratio <1 favors abiraterone acetate. | ||||||||||
Figure 7: Kaplan-Meier Plot of rPFS; ITT Population (Study PCR3011)
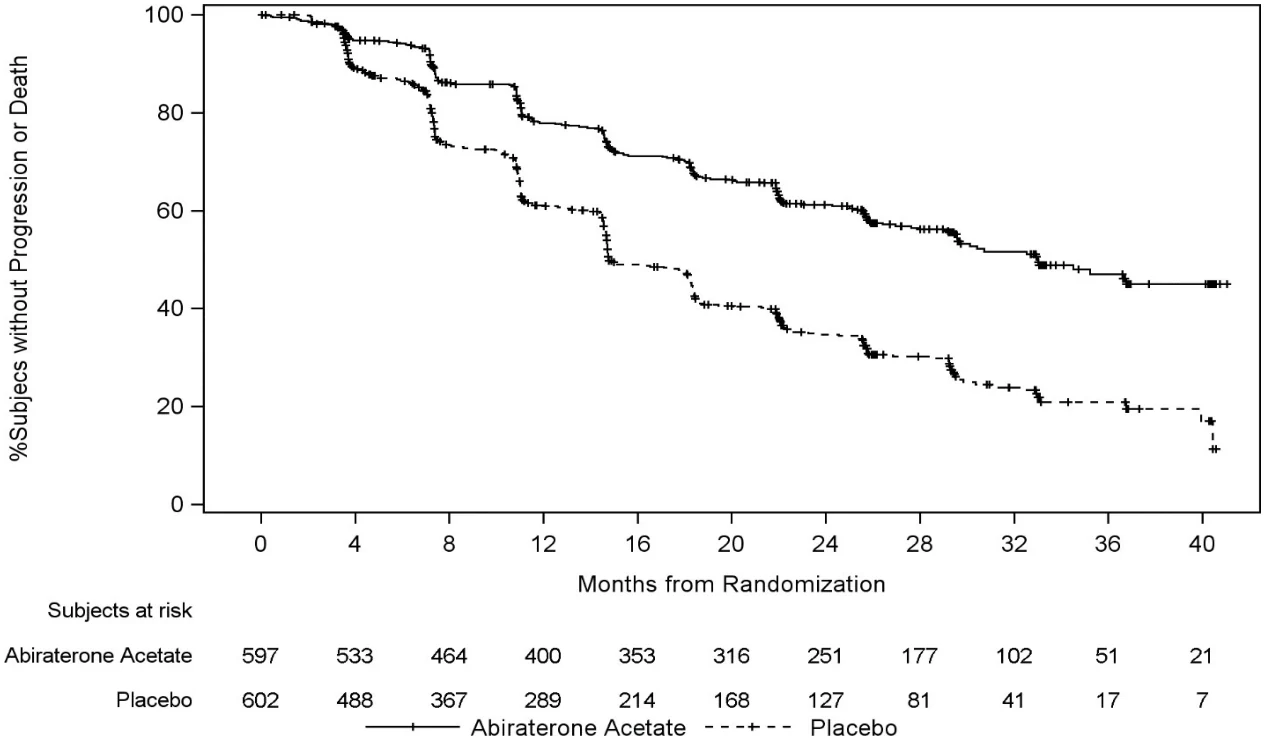
Figure 8: rPFS by Subgroup; ITT population (Study PCR3011)
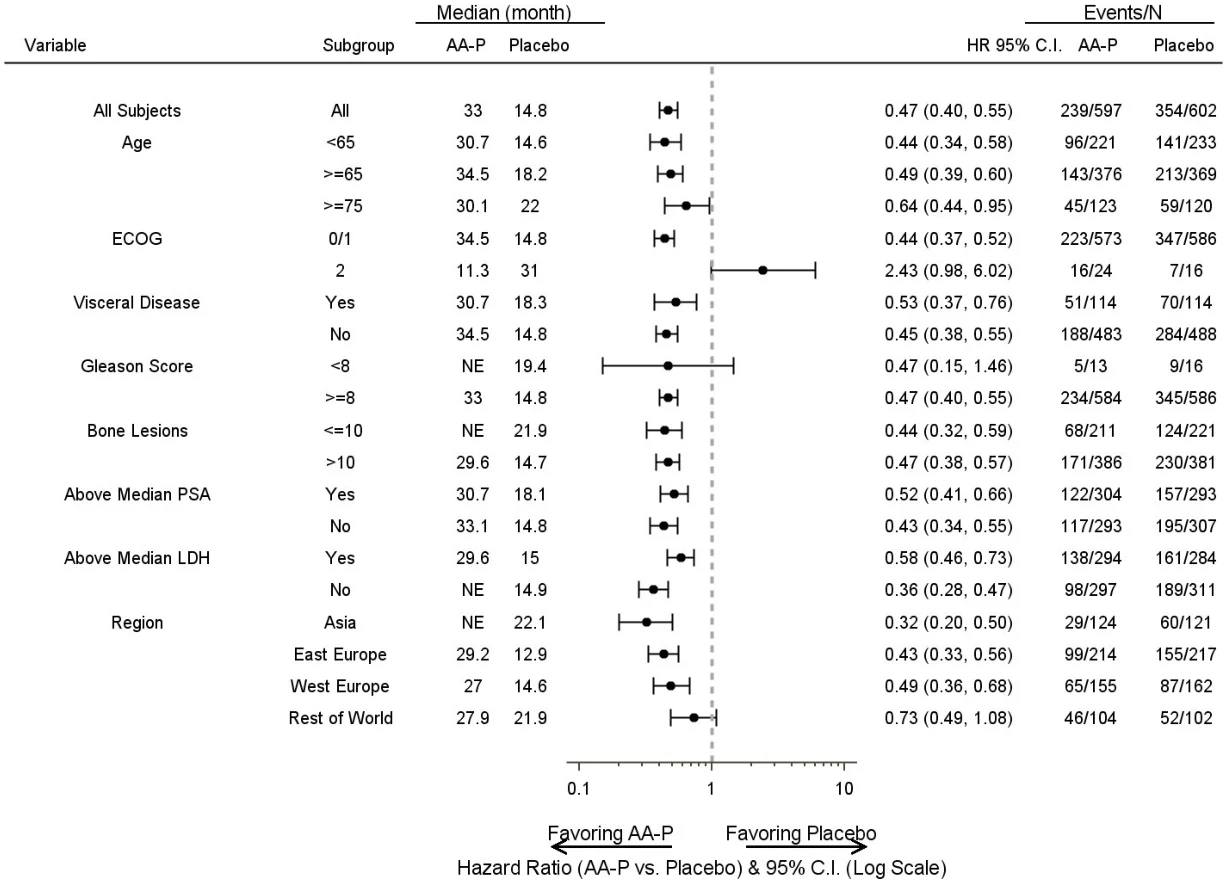
AA-P = abiraterone acetate + Prednisone
At the planned first interim analysis (IA-1) for overall survival, four hundred and six deaths had occurred. A statistically significant improvement in OS in favor of abiraterone acetate plus ADT was observed (Table 14). The study was unblinded based on the results of the interim OS analysis and patients in the placebo group were offered treatment with abiraterone acetate. Survival continued to be followed after this IA.
As of the clinical cut-off for the final analysis, 618 deaths were reported: 275 (46%) in the abiraterone acetate plus ADT group and 343 (57%) in the placebo group. The median follow-up time for all patients was 51.8 months. Significant improvement in OS was demonstrated in the abiraterone acetate treated group compared with the placebo group, showing a consistent and robust treatment effect in favor of abiraterone acetate treatment (Table 14, Figure 9). OS analysis by subgroups is shown in Figure 10.
| Table 14: Overall Survival, Stratified Analysis; ITT Population (Study PCR3011) | ||||||||||
| Abiraterone Acetate + Prednisone | Placebo | |||||||||
| N=597 | N=602 | |||||||||
| Interim Analysis | ||||||||||
| Event | 169 (28.3%) | 237 (39.4%) | ||||||||
| Median Survival (months) (95% CI) | NE (NE, NE) | 34.73 (33.05, NE) | ||||||||
| Hazard ratio (95% CI)b | 0.621 (0.509, 0.756) | |||||||||
| p valuea | <0.0001 | |||||||||
| Final Analysis | ||||||||||
Event Median Survival (months) (95% CI) Hazard ratio (95% CI)b p valuea | 275 (46.1%) 343 (57.0%) 53.32 (48.23, NE) 36.53 (33.54, 39.95) 0.661 (0.564, 0.775) <0.0001 | |||||||||
+=censored observation, NE=not estimable. a p value is from log-rank test stratified by ECOG PS score (0/1 or 2) and visceral (absent or present). b Hazard ratio is from stratified proportional hazards model. Hazard ratio <1 favors ZYTGA®. | ||||||||||
Figure 9: Kaplan-Meier Plot of Overall Survival; ITT Population (Study PCR3011)
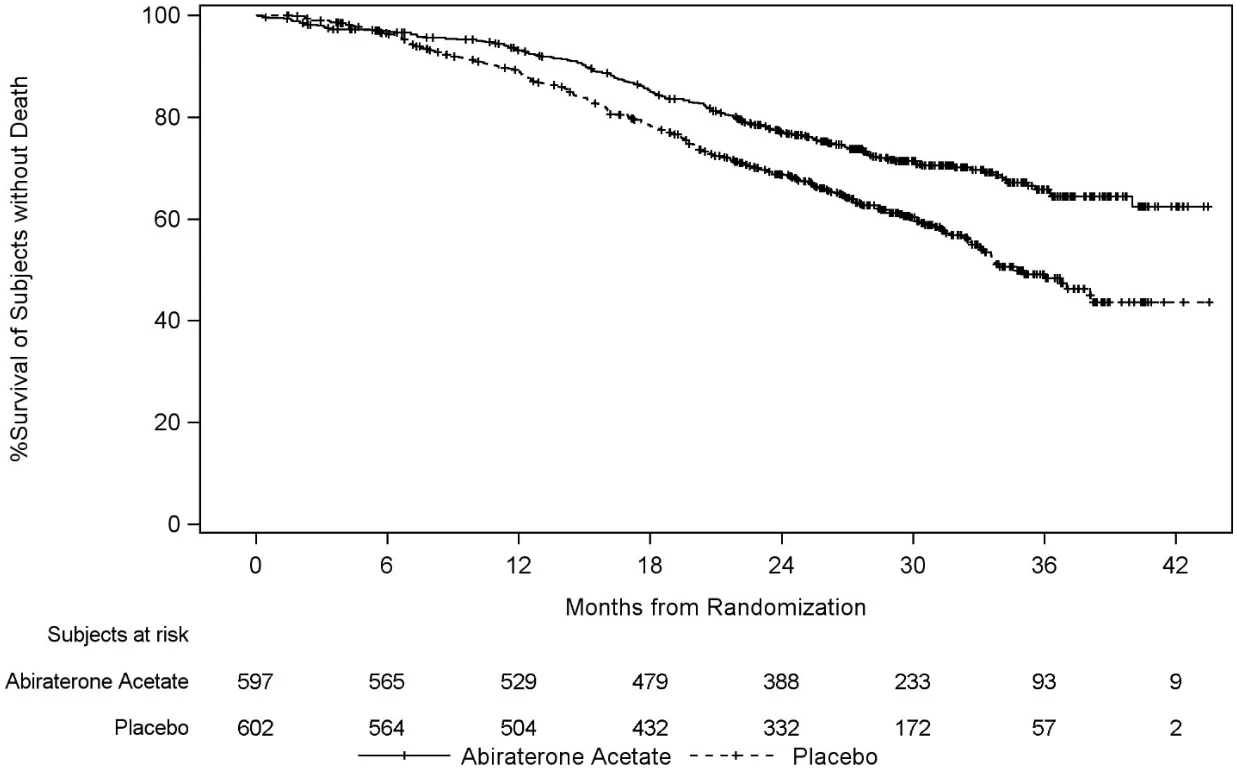
Figure 10: Overall Survival by Subgroup; ITT population (Study PCR3011)
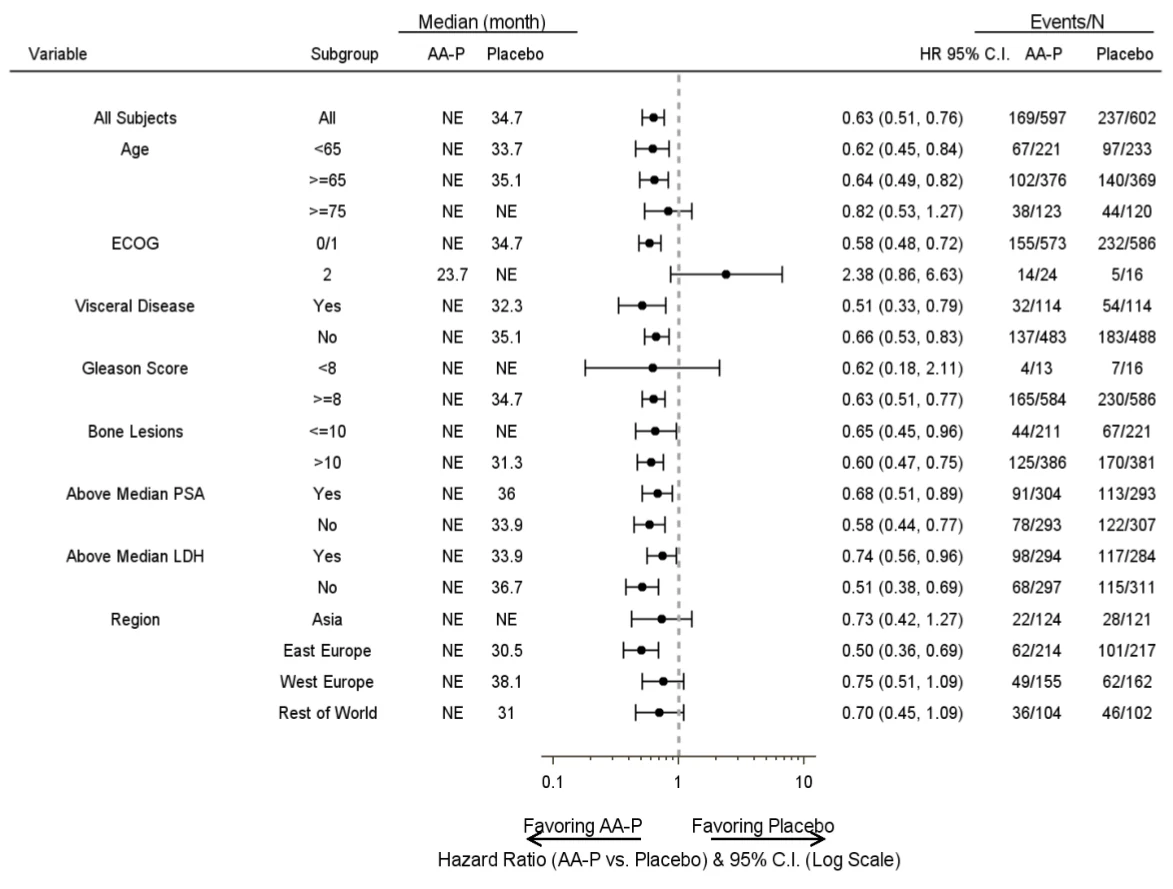
AA-P = abiraterone acetate +Prednisone
The Secondary endpoint measures at the time of the final analysis were as follows:
Time to skeletal-related event (SRE): Time to skeletal-related event was defined as the earliest of the following: clinical or pathological fracture, spinal cord compression, palliative radiation to bone, or surgery to bone. Skeletal-related events were reported for 22% of patients on abiraterone acetate and 25% on placebo. There was a 24% reduction in the risk of skeletal-related events (HR=0.759; 95% CI: [0.601, 0.960]; p<0.0208). The median time to SRE has not been reached for the abiraterone or placebo study arm.
Time to PSA progression based on PCWG2 criteria: Time to PSA progression was defined as the time interval from the date of randomization to the date of PSA progression, according to Prostate Cancer Working Group 2 (PCWG2) criteria. The median time to PSA progression based on PCWG2 criteria was 33.3 months for patients receiving abiraterone acetate and 7.4 months for patients receiving placebo (HR=0.310; 95% CI: [0.266, 0.363]; p<0.0001).Time to subsequent therapy for prostate cancer: Forty one percent of patients treated with abiraterone acetate and 59% of patients treated with placebo, received subsequent therapies that had the potential to prolong OS for this patient population. The median time to subsequent therapy was 54.9 months in the abiraterone acetate plus ADT group and was 21.2 months in the placebo group (HR=0.448; 95% CI: 0.380, 0.528; p<0.0001). Subsequent therapies included docetaxel (24% and 35% of patients treated with abiraterone acetate and placebo, respectively), enzalutamide (9% and 16%), cabazitaxel (4% and 8%), radium-223 dichloride (4% and 7%), and abiraterone acetate (3% and 14%).
Time to initiation of chemotherapy: Time to initiation of chemotherapy was defined as the time interval from the date of randomization to the date of initiation of chemotherapy for prostate cancer. The median time to initiation of chemotherapy was not reached for patients receiving abiraterone acetate and was 57.6 months for patients receiving placebo (HR=0.508; 95% CI: [0.412, 0.627]; p<0.0001).
Time to pain progression:
Time to pain progression was defined as the time interval from randomization to the first date a subject experienced a ≥30% increase from baseline in the Brief Pain Inventory – Short Form (BPI-SF) worst pain intensity (Item 3) observed at 2 consecutive evaluations ≥4 weeks apart. Pain progression was reported in 41% of patients on abiraterone acetate and 49% of patients on placebo. The median time to pain progression was 47.4 months for patients receiving abiraterone acetate and 16.6 months for patients receiving placebo (HR=0.721; 95% CI: [0.607, 0.857], p<0.0002).
DETAILED PHARMACOLOGY
Non-clinical pharmacokinetics
Several isoenzymes (CYP, UGT and SULT) are responsible for the metabolism of abiraterone into 15 detectable metabolites, accounting for approximately 92% of circulating radioactivity. CYP3A4 and SULT2A1 are the major single isoenzymes involved in metabolite formation with a minor contribution from UGT1A4, SULT1E1 and UGT1A3.
In vitro studies with human hepatic microsomes demonstrated that abiraterone was not an inhibitor for human CYP2A6 and CYP2E1. In these same studies, abiraterone was a moderate inhibitor of CYP2C9, CYP2C19 and CYP3A4/5. However, the concentrations of abiraterone in patients were lower than the concentration required for clinically meaningful inhibition of these enzymes. Abiraterone was also determined in vitro to be a potent inhibitor of CYP1A2, CYP2D6 and CYP2C8 (see Drug-Drug Interactions).
The pharmacokinetics of abiraterone in the presence of strong inducers or inhibitors of the above enzymes have not been evaluated in vitro or in vivo with the exception of CYP3A4 (see Drug- Drug Interactions, CYP3A4 inducers and CYP3A4 inhibitors).
TOXICOLOGY
In 13- and 26- week repeated dose studies in rats and 13- and 39-week repeated dose studies in monkeys, a reduction in circulating testosterone levels occurred with abiraterone at approximately one half the human clinical exposure based on AUC. As a result, morphological and/or histopathological changes were observed in the reproductive organs. These included aspermia/hypospermia, atrophy/weight reductions in the male genital tract organs and testes. In addition, adrenal gland hypertrophy, Leydig cell hyperplasia, pituitary gland hyperplasia and mammary gland hyperplasia were observed. The changes in the reproductive organs and androgen-sensitive organs are consistent with the pharmacology of abiraterone. All treatment- related changes were partially or fully reversed after a four-week recovery period.
After chronic treatment from 13 weeks onward, hepatocellular hypertrophy was observed in rats only at exposure levels of abiraterone 0.72-fold the human clinical exposure based on AUC. Bile duct/oval cell hyperplasia, associated with increased serum alkaline phosphatase and/or total bilirubin levels, was seen in the liver of rats (at exposure levels of abiraterone 3.2-fold the human clinical exposure based on AUC) and monkeys (at exposure levels of abiraterone 1.2-fold the human clinical exposure based on AUC). After a four-week recovery period, serum parameters reversed, whereas bile duct/oval cell hyperplasia persisted.
A dose dependent increase in cataracts was observed after 26 weeks of treatment in rats at exposure levels of abiraterone 1.1 times the human clinical exposure based on AUC. These changes were irreversible after a four-week recovery period. Cataracts were not observed in monkeys after 13 or 39 weeks of treatment at exposure levels 2-fold greater than the clinical exposure based on AUC.
Reproductive Toxicology
In fertility studies in rats, reduced organ weights of the reproductive system, sperm counts, sperm motility, altered sperm morphology and decreased fertility were observed in males dosed for 4 weeks at ≥ 30 mg/kg/day. Mating of untreated females with males that received 30 mg/kg/day abiraterone acetate resulted in a reduced number of corpora lutea, implantations and live embryos and an increased incidence of pre-implantation loss. Effects on male rats were reversible after 16 weeks from the last abiraterone acetate administration. Female rats dosed for 2 weeks until day 7 of pregnancy at ≥ 30 mg/kg/day had an increased incidence of irregular or extended estrous cycles and pre-implantation loss (300 mg/kg/day). There were no differences in mating, fertility, and litter parameters in female rats that received abiraterone acetate. Effects on female rats were reversible after 4 weeks from the last abiraterone acetate administration. The dose of 30 mg/kg/day in rats is approximately 0.3 times the recommended dose of 1000 mg/day based on body surface area.
In developmental toxicity study in rats, although abiraterone acetate did not have teratogenic potential, abiraterone acetate caused developmental toxicity when administered at doses of 10, 30 or 100 mg/kg/day throughout the period of organogenesis (gestational days 6 to 17). Findings included embryo-fetal lethality (increased post-implantation loss and resorptions and decreased number of live fetuses), fetal developmental delay (skeletal effects) and urogenital effects (bilateral ureter dilation) at doses ≥ 10 mg/kg/day, decreased fetal ano-genital distance at ≥30 mg/kg/day, and decreased fetal body weight at 100 mg/kg/day. Doses ≥ 10 mg/kg/day caused maternal toxicity. The doses (10, 30, or 100 mg/kg) tested in rats resulted in systemic exposures (AUC) approximately 0.03, 0.1 and 0.3 times, respectively, the AUC in patients.
APO-ABIRATERONE ACETATE FILM COATED TABLETS is contraindicated in pregnancy (see CONTRAINDICATIONS and WARNINGS AND PRECAUTIONS, Special Populations).
Carcinogenesis and Genotoxicity
Abiraterone acetate was not carcinogenic in a 6-month study in the transgenic (Tg.rasH2) mouse. In a 24-month carcinogenicity study in the rat, abiraterone acetate increased the incidence of interstitial cell neoplasms in the testes. This finding is considered related to the pharmacological action of abiraterone. The clinical relevance of this finding is not known. Abiraterone acetate was not carcinogenic in female rats.
Abiraterone acetate and abiraterone were devoid of genotoxic potential in the standard panel of genotoxicity tests, including an in vitro bacterial reverse mutation assay (the Ames test), an in vitro mammalian chromosome aberration test (using human lymphocytes) and an in vivo rat micronucleus assay.
REFERENCES
- 1. Attard G, Reid AHM and de Bono JS. Abiraterone acetate is well tolerated without concomitant use of corticosteroids. J Clin Oncol 2010;29:5170–1.
- 2. Attard G, Reid AHM, Yap TA, et al. Phase I clinical trial of a selective inhibitor of CYP17, abiraterone acetate, confirms that castration-resistant prostate cancer commonly remains hormone driven. J Clin Oncol 2008;26:4563–71.
- 3. Attard G, Reid AHM, A'Hern R, et al. Selective inhibition of CYP17 with abiraterone acetate is highly active in the treatment of castration-resistant prostate cancer. J Clin Oncol 2009;27:3742–8.
- 4. Danila DC, Morris MJ, de Bono JS, et al. Phase II multicenter study of abiraterone acetate plus prednisone therapy in patients with docetaxel-treated, castration-resistant prostate cancer. J Clin Oncol 2010;28:1496–1501.
- 5. de Bono JS, Logothetis CJ, Molina A, et al. Abiraterone and increased survival in metastatic prostate cancer. N Engl J Med 2011;364(21):1995–2005.
- 6. James ND, de Bono JS, Spears MR, et al. Abiraterone for Prostate Cancer Not Previously Treated with Hormone Therapy. N Engl J Med. 2017 Jun 3 [epub ahead of print].
- 7. Luthy A, Begin DJ and Labrie F. Androgenic activity of synthetic progestins and spironolactone in androgen-sensitive mouse mammary carcinoma (Shionogi) cells in culture. J Steroid Biochem 1988;31(5):845–52.
- 8. Ryan CJ, Smith MR, Fong L, et al. Phase I clinical trial of the CYP17 inhibitor abiraterone acetate demonstrating clinical activity in patients with castration-resistant prostate cancer who received prior ketoconazole therapy. J Clin Oncol 2010;28(9):1481–8.
- 9. Ryan CJ, Smith MR, de Bono JR, et al. Abiraterone in metastatic prostate cancer without previous chemotherapy. N Engl J Med 2013;368:138–48.
- 10. Product Monograph - ZYTIGA® (Abiraterone acetate tablets) 250 mg and 500 mg. Janssen Inc., Date of Revision: January 4, 2021, Control Number: 244273