


Product Monograph - Apo-Lamivudine Hbv
RECENT MAJOR LABEL CHANGES
None
TABLE OF CONTENTS
Sections or subsections that are not applicable at the time of authorization are not listed.
RECENT MAJOR LABEL CHANGES .......................................................................................... 2
TABLE OF CONTENTS ............................................................................................................ 2
PART I: HEALTH PROFESSIONAL INFORMATION .................................................................... 4
1 INDICATIONS ............................................................................................................ 4
1.1 Pediatrics (<16 years of age) .................................................................................... 4
1.2 Geriatrics (> 65 years of age) .................................................................................... 4
2 CONTRAINDICATIONS .............................................................................................. 4
3 SERIOUS WARNINGS AND PRECAUTIONS BOX ........................................................... 5
4 DOSAGE AND ADMINISTRATION ................................................................................ 5
4.1 Dosing Considerations .............................................................................................. 5
4.2 Recommended Dose and Dosage Adjustment ......................................................... 5
4.4 Administration .......................................................................................................... 6
4.5 Missed Dose .............................................................................................................. 6
5 OVERDOSAGE ............................................................................................................ 6
6 DOSAGE FORMS, STRENGTHS, COMPOSITION AND PACKAGING ................................ 7
7 WARNINGS AND PRECAUTIONS ................................................................................. 7
7.1 Special Populations ................................................................................................. 10
7.1.1 Pregnant Women ........................................................................................ 10
7.1.2 Breast-feeding ............................................................................................. 11
7.1.3 Pediatrics..................................................................................................... 11
7.1.4 Geriatrics ..................................................................................................... 11
8 ADVERSE REACTIONS ............................................................................................... 11
8.2 Clinical Trial Adverse Reactions .............................................................................. 11
8.5 Post-Market Adverse Reactions ............................................................................. 13
9 DRUG INTERACTIONS .............................................................................................. 14
9.2 Drug Interactions Overview .................................................................................... 14
9.4 Drug-Drug Interactions ........................................................................................... 15
9.5 Drug-Food Interactions ........................................................................................... 16
9.6 Drug-Herb Interactions ........................................................................................... 16
9.7 Drug-Laboratory Test Interactions ......................................................................... 17
10 CLINICAL PHARMACOLOGY ...................................................................................... 17
10.1 Mechanism of Action .............................................................................................. 17
10.2 Pharmacodynamics ................................................................................................. 17
10.3 Pharmacokinetics.................................................................................................... 17
11 STORAGE, STABILITY AND DISPOSAL ........................................................................ 19
12 SPECIAL HANDLING INSTRUCTIONS .......................................................................... 19
PART II: SCIENTIFIC INFORMATION .................................................................................... 20
13 PHARMACEUTICAL INFORMATION ........................................................................... 20
14 CLINICAL TRIALS ...................................................................................................... 21
14.1 Clinical Trials by Indication ..................................................................................... 21
14.2 Comparative Bioavailability Studies ....................................................................... 24
15 MICROBIOLOGY ....................................................................................................... 25
16 NON-CLINICAL TOXICOLOGY .................................................................................... 26
17 SUPPORTING PRODUCT MONOGRAPHS ................................................................... 28
PATIENT MEDICATION INFORMATION ................................................................................ 29
PART I: HEALTH PROFESSIONAL INFORMATION
1 INDICATIONS
APO-LAMIVUDINE HBV (lamivudine) is indicated for the treatment of patients with chronic hepatitis B and evidence of hepatitis B virus (HBV) replication.
This indication is based on the analysis of histologic and serologic endpoints in patients with compensated chronic hepatitis B, which were mainly derived from studies of one year duration (see 14 CLINICAL TRIALS, Study Results). Data beyond one year are limited. The safety and efficacy of lamivudine tablets have not been established in patients with decompensated liver disease in placebo controlled studies.
The following point should be considered when initiating therapy with APO-LAMIVUDINE HBV:
Due to high rates of resistance development in treated patients, initiation of lamivudine treatment should only be considered when the use of an alternative antiviral agent with a higher genetic barrier to resistance is not available or appropriate.
Studies in patients with chronic hepatitis B have shown that compared to placebo, lamivudine tablets therapy can produce improvements in liver necro-inflammatory activity, increased HBeAg seroconversion, suppression of HBV DNA, and/or normalisation of serum aminotransferase.
1.1 Pediatrics (<16 years of age)
No data are available to Health Canada; therefore, Health Canada has not authorized an indication for pediatric use.
1.2 Geriatrics (> 65 years of age)
Clinical studies of lamivudine tablets did not include sufficient numbers of patients aged 65 and older to determine whether they respond differently from younger subjects. In general, dose selection for an elderly patient should be cautious, reflecting the greater frequency of decreased hepatic, renal or cardiac function, and of concomitant disease or other drug therapy (see 7 WARNINGS AND PRECAUTIONS).
2 CONTRAINDICATIONS
APO-LAMIVUDINE HBV is contraindicated in patients who previously demonstrated clinically significant hypersensitivity to any of the components of the products (see the 6 DOSAGE FORMS, STRENGTHS, COMPOSITION AND PACKAGING, Table 1).
3 SERIOUS WARNINGS AND PRECAUTIONS BOX
Serious Warnings and Precautions
Patients coinfected with HIV and HBV should be closely monitored with both clinical and laboratory follow-up for at least several months after stopping treatment with lamivudine tablets 100 mg. |
|---|
4 DOSAGE AND ADMINISTRATION
4.1 Dosing Considerations
Discontinuation of lamivudine tablets may be considered in immunocompetent patients when HBeAg and/or HBsAg seroconversion occurs and when loss of efficacy occurs as indicated by recurrent signs of hepatitis. There are limited data regarding the maintenance of seroconversion long term after stopping treatment with lamivudine tablets. If lamivudine tablets are discontinued, patients should be periodically monitored for evidence of recurrent hepatitis (See 7 WARNINGS AND PRECAUTIONS, Immune).
The formulation and dosage of lamivudine in APO-LAMIVUDINE HBV 100 mg tablets are not appropriate in patients dually infected with Hepatitis B and HIV. If lamivudine is administered to such patients, the higher dosage indicated for HIV therapy should be used as part of a combination treatment regimen and the Product Monographs for Lamivudine 150 mg and 300 mg tablets and Lamivudine 100 mg tablets should be consulted.
4.2 Recommended Dose and Dosage Adjustment
The recommended dose of APO-LAMIVUDINE HBV for adults and adolescents who are 16 years and older is 100 mg lamivudine once daily (one tablet). Optimum duration of therapy has not been established.
Hepatic Insufficiency
No dose adjustment is necessary in patients with hepatic impairment unless accompanied by renal impairment.
Renal Insufficiency
Lamivudine serum concentrations are increased in patients with moderate to severe renal impairment due to decreased renal clearance. The dosage should therefore be reduced for patients with a creatinine clearance of < 50 mL/min. When doses below 100 mg are required Lamivudine 5 mg/ mL oral solution should be used (see table below).
Creatinine clearance mL/min | First Dose of lamivudine oral solution* | Maintenance Dose Once Daily |
|---|---|---|
| 30 to < 50 | 20 mL (100 mg) | 10 mL (50 mg) |
| 15 to < 30 | 20 mL (100 mg) | 5 mL (25 mg) |
| 5 to < 15 | 7 mL (35 mg) | 3 mL (15 mg) |
| < 5 | 7 mL (35 mg) | 2 mL (10 mg) |
* Oral Solution containing 5mg/mL lamivudine.
Data available in patients undergoing intermittent hemodialysis (≤ 4 hours dialysis 2 to 3 times weekly), indicate that following the initial dosage reduction of lamivudine to correct for the patient’s creatinine clearance, no further dosage adjustments are required while undergoing dialysis.
4.4 Administration
APO-LAMIVUDINE HBV can be taken with or without food.
4.5 Missed Dose
If the patient forgets to take their medicine, they should take it as soon as they remember, then continue as before.
5 OVERDOSAGE
For management of a suspected drug overdose, contact your regional poison control centre.
No specific signs or symptoms have been identified following acute overdose with lamivudine, apart from those listed as adverse reactions.
If overdose occurs the patient should be monitored and standard supportive treatment applied.
Although no data is available, administration of activated charcoal may be used to aid in removal of unabsorbed drug. Since lamivudine is dialysable, continuous hemodialysis could be used in the treatment of overdose, although this has not been studied.
6 DOSAGE FORMS, STRENGTHS, COMPOSITION AND PACKAGING
Table 1 – Route of Administration, Dosage Forms/Strengths, and Non-medicinal Ingredients
| Route of Administration | Dosage Form / Strength | Non-medicinal Ingredients |
| Oral | Tablets / 100 mg | colloidal silicon dioxide, crospovidone, hydroxypropyl cellulose, hydroxypropyl methylcellulose, lactose anhydrous, magnesium stearate, polyethylene glycol, red ferric iron oxide #34690, titanium dioxide and yellow ferric oxide. |
Dosage Forms and Packaging
APO-LAMIVUDINE HBV (lamivudine) 100 mg tablets: Each orange-brown, capsule shaped, biconvex film coated tablet, engraved “APO” on one side and “LMV 100” on the other side contains lamivudine methanol solvate equivalent to 100 mg lamivudine. Available in bottles of 60 and 100 tablets.
7 WARNINGS AND PRECAUTIONS
Please see the 3 SERIOUS WARNINGS AND PRECAUTIONS BOX at the beginning of Part I: Health Professional Information.
General
Patients should be monitored at initiation of treatment and regularly during maintenance of treatment by a physician experienced in the management of chronic hepatitis B.
Optimum duration of therapy has not been established.
The efficacy of lamivudine has not been established in patients not responding to alpha-interferon therapy.
Chronic hepatitis B is a highly variable condition and it is possible the patient may experience rebound during therapy (i.e. viral load increase or increase in liver enzyme levels) or other discordant results (e.g. increased HBV DNA and improved liver histology). Since there are no strong correlations between serological and histological markers of response, the decision on whether or not to continue lamivudine tablets therapy should be based on clinical status and serological marker trends rather than a single result.
Patients should be advised that therapy of chronic hepatitis B, with lamivudine tablets has not been proven to reduce the risk of transmission of hepatitis B virus to others through sexual contact or blood contamination and therefore, appropriate precautions should still be taken.
Several serious adverse events have been reported with use of lamivudine in HIV-infected patients. Reports of anaphylaxis, rhabdomyolysis and peripheral neuropathy have been rare (< 1 in 1000).
Hematologic
Lamivudine use at higher doses in HIV disease has resulted in very rare occurrences of pure red cell aplasia. To date no definitive occurrences have been seen in hepatitis B patients at the recommended dose.
Hepatic/Biliary/Pancreatic
The safety and efficacy of lamivudine tablets have not been established in patients with decompensated liver disease.
Patients with marginal liver function are at greater risk from active viral replication. In these patients, hepatitis reactivation at discontinuation of lamivudine or loss of efficacy during treatment may induce severe and even fatal decompensation. It is recommended that these patients are monitored for parameters associated with hepatitis B, for liver and renal functions, and for antiviral response during treatment. If treatment is discontinued for any reason, it is recommended that these patients are monitored closely for at least 6 months after cessation of treatment.
- Lactic Acidosis/Severe Hepatomegaly with Steatosis
Lactic acidosis and severe hepatomegaly with steatosis, including fatal cases, have been reported with the use of antiretroviral nucleoside analogues alone or in combination, including lamivudine, in the treatment of HIV infection. A majority of these cases have been in women. Female sex and obesity may be risk factors. Most of these reports have described patients receiving nucleoside analogues for the treatment of HIV infection, but there have been rare reports of lactic acidosis in patients receiving lamivudine for hepatitis B. Particular caution should be exercised when administering Lamivudine 150 mg and 300 mg tablets or Lamivudine 100 mg tablets to any patient with known risk factors for liver disease (other than hepatitis B). However, cases have been reported in patients with no known risk factors. Treatment with lamivudine tablets should be suspended in any patient who develops clinical or laboratory findings suggestive of lactic acidosis or pronounced hepatotoxicity.
- Pancreatitis
Pancreatitis has been reported in patients receiving Lamivudine tablets 150 mg and 300 mg (lamivudine), particularly in HIV-infected pediatric patients with prior nucleoside exposure.
Immune
In HBeAg positive or negative patients, the development of YMDD (tyrosine-methionineaspartate-aspartate) mutant HBV may result in a diminished therapeutic response to lamivudine, indicated by a rise in HBV DNA and ALT from previous on-treatment levels. In order to reduce the risk of resistance in patients receiving lamivudine monotherapy, a switch to or addition of an alternative agent without cross-resistance to lamivudine should be considered if serum HBV DNA remains detectable at or beyond 24 weeks of treatment.
If lamivudine tablets are discontinued or there is a loss of efficacy, some patients may experience clinical or laboratory evidence of recurrent hepatitis. Exacerbation of hepatitis has primarily been detected by serum ALT elevations, in addition to the re-emergence of HBV DNA. Most events appear to have been self-limited. Fatalities due to exacerbation of hepatitis after discontinuation of lamivudine tablets are uncommon.
Some chronic hepatitis B patients may be coinfected with HIV. The possibility of such co-infection should be considered prior to initiating lamivudine tablets therapy. Co-infected patients receiving or requiring an antiretroviral treatment regimen including lamivudine for HIV should be treated with the dose of lamivudine usually recommended for HIV infection.
For coinfected patients not requiring antiretroviral therapy, the benefit of using lamivudine for treating chronic hepatitis B needs to be weighed against the potential compromise of a therapeutic option to subsequent progressive HIV and the possible emergence of drug resistant HIV.
There are no clinical data on the efficacy of lamivudine in patients < 16 years of age or co-infected with Delta hepatitis.
Monitoring and Laboratory Tests
If APO-LAMIVUDINE HBV is discontinued, patients should be periodically monitored both clinically and by assessment of serum liver function tests (ALT and bilirubin levels), for at least four months for evidence of recurrent hepatitis; patients should then be followed as clinically indicated. For patients who develop evidence of recurrent hepatitis post-treatment, there are insufficient data on the benefits of re-initiation of APO-LAMIVUDINE HBV treatment.
Renal
Patients With Impaired Renal Function
In patients with moderate to severe renal impairment, serum lamivudine concentrations are increased due to decreased renal clearance, therefore the dose should be reduced for patients with a creatinine clearance of < 50 mL/min (see 4.2 Recommended Dose and Dosage Adjustment, Renal Insufficiency).
7.1 Special Populations
7.1.1 Pregnant Women
Lamivudine has not been studied in pregnant women. Use in pregnancy should be considered only if the benefit outweighs the risk.
In the phase III clinical studies, 15 pregnancies have been reported in patients receiving lamivudine for chronic hepatitis B: 2 were terminated in elective abortions, 11 were normal live births, and the outcome is unknown in 2. One of the 11 normal births was later found to have a mitral valve prolapse, which was not regarded as related to lamivudine by the investigator.
Although the results of animal studies (see 16 NON-CLINICAL TOXICOLOGY, Reproductive and Developmental Toxicology) are not always predictive of human response, there was no evidence of teratogenicity in animals, but findings in the rabbit suggest a potential risk of early embryonic loss that was not observed in the rat.
For patients who are on treatment with lamivudine tablets and subsequently become pregnant, consideration should be given to the possibility of a recurrence of hepatitis upon discontinuation of lamivudine tablets.
Based on the limited data, it has not been established whether lamivudine can prevent the maternal-fetal transmission of hepatitis B virus in pregnant women receiving treatment with lamivudine tablets. The standard recommended procedures for hepatitis B virus immunization in infants should be followed.
Pregnancy Registry: To monitor maternal-fetal outcomes of pregnant women exposed to APO-LAMIVUDINE HBV, a Pregnancy Registry has been established. Physicians are encouraged to register patients by calling Antiretroviral Pregnancy Registry at 1-800-258-4263..
There are no adequate and well-controlled trials in pregnant women and the safe use of lamivudine in pregnancy has not been established. The Antiretroviral Pregnancy Registry has received reports of over 11,000 exposures (including over 4500 exposures during the first trimester) to lamivudine during pregnancy resulting in live birth. Less than 1% of these women have been treated for HBV, whereas the majority were treated for HIV at higher doses. There was no difference between overall birth defects associated with lamivudine compared to the overall background birth defect rate of 2.7%.
7.1.2 Breast-feeding
Following repeat oral administration of either 150 mg or 300 mg, lamivudine twice daily, lamivudine was excreted in breast milk (0.5 to 8.2 mcg/mL) at similar concentrations to those found in serum. In other studies following repeat oral administration of 150 mg lamivudine twice daily, the breast milk: maternal plasma ratio ranged between 0.6 and 3.3. Lamivudine median infant serum concentrations ranged between 18 and 28 ng/mL and were not detectable in one of the studies (assay sensitivity 7 ng/mL). The clinical relevance of this finding is unknown. It is recommended that mothers taking lamivudine do not breast feed to avoid potential adverse effects from lamivudine in nursing infants.
Lamivudine should only be used in a nursing mother if the expected benefit justifies the potential risk to the infant. A decision must be made whether to discontinue breast feeding or to discontinue/abstain from lamivudine therapy, taking into account the benefit of breast feeding for the child and the benefit of therapy for the woman.
7.1.3 Pediatrics
Pediatrics (< 16 years of age): There are no clinical data on the efficacy of lamivudine in patients < 16 years of age or coinfected with Delta hepatitis.
7.1.4 Geriatrics
(≥65 years of age): Clinical studies of lamivudine tablets did not include sufficient numbers of subjects aged 65 and over to determine whether they respond differently from younger subjects. In general, dose selection for an elderly patient should be cautious, reflecting the greater frequency of decreased hepatic, renal, or cardiac function, and of concomitant disease or other drug therapy. In particular, because lamivudine is substantially excreted by the kidney and elderly patients are more likely to have decreased renal function, renal function should be monitored and dosage adjustments should be made accordingly (see 7 WARNINGS AND PRECAUTIONS, Renal and 4.2 Recommended Dose and Dosage Adjustment, Renal Insufficiency).
8 ADVERSE REACTIONS
8.2 Clinical Trial Adverse Reactions
Clinical trials are conducted under very specific conditions. The adverse reaction rates observed in the clinical trials; therefore, may not reflect the rates observed in practice and should not be compared to the rates in the clinical trials of another drug. Adverse reaction information from clinical trials may be useful in identifying and approximating rates of adverse drug reactions in real-world use.
In clinical studies of patients with chronic hepatitis B, lamivudine was well tolerated. The incidence of adverse events was similar between placebo and lamivudine treated patients. The most common adverse events reported were malaise and fatigue, respiratory tract infections, headache, abdominal discomfort and pain, nausea, vomiting and diarrhea. The most common adverse events (≥ 5%), reported in three pivotal trials (NUCB3009, NUCA3010 and NUCB3010) during treatment, are summarized in the table below:
| Most Common Adverse Events | No. (%) of Patients | |
|---|---|---|
PLA n = 144 | LAM100 mg n = 297 | |
| During Treatment | ||
| Malaise and fatigue | 36 (25%) | 73 (25%) |
| Headache | 30 (21%) | 63 (21%) |
| Viral respiratory infection | 26 (18%) | 61 (21%) |
| Abdominal discomfort and pain | 25 (17%) | 41 (14%) |
| Diarrhea | 18 (13%) | 41 (14%) |
| Cough | 14 (10%) | 35 (12%) |
| ENT infections | 15 (10%) | 35 (12%) |
| Nausea and vomiting | 20 (14%) | 43 (14%) |
| Throat and tonsil discomfort and pain | 12 (8%) | 35 (12%) |
| Viral ear nose & throat infections | 15 (10%) | 29 (10%) |
| Musculoskeletal pain | 14 (10%) | 23 (8%) |
| Nasal signs & symptoms | 10 (7%) | 23 (8 %) |
| Dizziness | 10 (7%) | 22 (7%) |
| Sleep disorders | 11 (8%) | 20 (7%) |
| Temperature regulations disturbances | 10 (7%) | 15 (5%) |
| Abnormal; enzyme levels | 8 (6%) | 16 (5%) |
The incidence of laboratory abnormalities in chronic hepatitis B patients were similar in the lamivudine and placebo treated groups with the exception of elevations of CK and
ALT. Elevations of CK (≥ 7 times baseline) were more common in the lamivudine treated group during treatment. Elevations of ALT (≥ 2 times baseline) were more common post-treatment in the lamivudine treated groups. In controlled trials, however, there was no appreciable difference post-treatment in clinically severe ALT elevations, associated with bilirubin elevations and/or signs of hepatic insufficiency, between lamivudine and placebo treated patients. The relationship of these recurrent hepatitis events to lamivudine treatment or to the previous underlying disease is uncertain (see 7 WARNINGS AND PRECAUTIONS, Hepatic/Biliary/Pancreatic).
In patients with HIV infection, cases of pancreatitis and peripheral neuropathy (or paraesthesia) have been reported, although no relationship to treatment with lamivudine (Lamivudine tablets 150 mg and 300 mg) has been clearly established. In patients with chronic hepatitis B there was no observed difference in incidence of these events between placebo and lamivudine 100 mg tablets treated patients.
Cases of lactic acidosis, usually associated with severe hepatomegaly and hepatic steatosis, have been reported with the use of combination nucleoside analogue therapy in patients with HIV. There have been occasional reports of these adverse events in hepatitis B patients with decompensated liver disease, however, the association of lamivudine with these events has not been established.
The following convention has been utilized for the classification of undesirable effects:
Very common (>1/10), common (>1/100, <1/10), uncommon (>1/1,000, <1/100), rare
(>1/10,000, <1/1,000), very rare (<1/10,000).
Hepatobiliary disorders
Very common: Elevations of ALT
Musculoskeletal and connective tissue disorders
Common: Elevations of CK
Skin and subcutaneous tissue disorders
Common: Rash, pruritus
Several serious adverse events reported with lamivudine (lactic acidosis and severe hepatomegaly with steatosis, posttreatment exacerbations of hepatitis B, pancreatitis, and emergence of viral mutants associated with reduced drug susceptibility and diminished treatment response) are also described in 7 WARNINGS AND PRECAUTIONS Hepatic/Biliary/Pancreatic.
8.5 Post-Market Adverse Reactions
The following events have been reported during therapy for HIV disease with lamivudine alone and in combination with other anti-retroviral agents. Because they are reported voluntarily from a population of unknown size, estimates of frequency cannot be made.
With many it is unclear whether they are related to the medicinal products or are as a result of the underlying disease process.
Blood and lymphatic systems disorders
Anaemia, neutropenia, pure red cell aplasia, thrombocytopenia, lymphadenopathy, splenomegaly
Metabolism and nutrition disorders
Hyperlactataemia, hyperglycemia, lactic acidosis (see in 7 WARNINGS AND PRECAUTIONS, Hepatic/Biliary/Pancreatic), redistribution/accumulation of body fat. The incidence of this event is dependent on multiple factors including the particular antiretroviral drug combination.
Nervous system disorders
Headache, paraesthesia, peripheral neuropathy
Gastrointestinal disorders
Diarrhea, nausea, pancreatitis, rises in serum amylase, upper abdominal pain, vomiting
Skin and subcutaneous tissue disorders
Alopecia
Musculoskeletal and connective tissue disorders
Arthralgia, muscle disorders, including myalgia and cramps, rhabdomyolysis
General disorders and administration site conditions
Fatigue, fever, malaise
Respiratory
Abnormal breath sounds/wheezing
9 DRUG INTERACTIONS
9.2 Drug Interactions Overview
The likelihood of metabolic interactions is low due to limited metabolism and plasma protein binding and almost complete renal elimination of unchanged drug.
Lamivudine is predominantly eliminated by active organic cationic secretion. The possibility of interactions with other drugs administered concurrently should be considered, particularly when their main route of elimination is active renal secretion via the organic cationic transport system (e.g. trimethoprim). Other drugs (e.g. ranitidine, cimetidine) are eliminated only in part by this mechanism and were shown not to interact with lamivudine.
Drugs shown to be predominately excreted either via the active organic anionic pathway, or by glomerular filtration are unlikely to yield clinically significant interactions with lamivudine.
Effect of other agents on the pharmacokinetics of lamivudine
Lamivudine is a substrate of MATE1, MATE2-K and OCT2 in vitro. Trimethoprim (an inhibitor of these drug transporters) when given in combination with sulphamethoxazole, has been shown to increase lamivudine plasma concentrations (see Table 2).
Lamivudine is a substrate of the hepatic uptake transporter OCT1. As hepatic elimination plays a minor role in the clearance of lamivudine, drug interactions due to inhibition of OCT1 are unlikely to be of clinical significance.
Lamivudine is an in vitro substrate of Pgp and BCRP, however due to its high bioavailability it is unlikely that these transporters play a significant role in the absorption of lamivudine. Therefore co-administration of drugs that are inhibitors of these efflux transporters is unlikely to affect the disposition and elimination of lamivudine.
Effect of lamivudine on the pharmacokinetics of other agents
In vitro, lamivudine demonstrates no or weak inhibition of the drug transporters organic anion transporter 1B1 (OATP1B1), OATP1B3, breast cancer resistance protein (BCRP) or P-glycoprotein (Pgp), multidrug and toxin extrusion protein 1 (MATE1), MATE2-K or organic cation transporter 3 (OCT3). Lamivudine is therefore not expected to affect the plasma concentrations of drugs that are substrates of these drug transporters.
Lamivudine is an inhibitor of OCT1 and OCT2 in vitro with IC50 values of 17 and 33 uM, respectively, however lamivudine has low potential to affect the plasma concentrations of OCT1 and OCT2 substrates at therapeutic drug exposures (up to 300 mg which is three times higher than the recommended maximum dose for HBV).
9.4 Drug-Drug Interactions
The drugs listed in this table are based on either drug interaction case reports or studies, or potential interactions due to the expected magnitude and seriousness of the interaction (i.e., those identified as contraindicated).
Table 2 Established or Potential Drug-Drug Interactions
| Proper name | Effect | Clinical comment |
|---|---|---|
Trimethoprim/ Sulphamethoxazole 160 mg/800 mg | Increased lamivudine exposure by about 40%. | Lamivudine had no effect on the pharmacokinetics of trimethoprim or sulphamethoxazole. Unless the patient has renal |
| Proper name | Effect | Clinical comment |
|---|---|---|
| impairment, no dosage adjustment of lamivudine is necessary. | ||
| Zidovudine | A modest increase in Cmax (28%) for zidovudine when administered with lamivudine. | Overall exposure (AUC) was not significantly altered. Zidovudine had no effect on the pharmacokinetics of lamivudine (See10.3 Pharmacokinectics). |
| Immunosuppressant drugs | There were no observed clinically significant adverse interactions in patients taking lamivudine concurrently with commonly used immunosuppressant drugs (e.g. cyclosporin A). | Formal interaction studies have not been performed. |
| Emtricitabine | Lamivudine may inhibit the intracellular phosphorylation of emtricitabine when the two medicinal products are used concurrently. | APO-LAMIVUDINE HBV is not recommended for use in combination with emtricitabine. |
| Sorbitol | Coadministration of sorbitol solution (3.2 g, 10.2 g, 13.4 g) with a single 300 mg dose (Adult HIV daily dose) of lamivudine oral solution resulted in dose-dependent decreases of 14%, 32%, and 36% in lamivudine exposure (AUC∞) and 28%, 52%, and 55% in the Cmax of lamivudine in adults. | When possible, avoid use of lamivudine with sorbitol-containing medicines or consider more frequent monitoring of HBV viral load when chronic coadministration cannot be avoided. |
| alpha-interferon | Lamivudine has no pharmacokinetic interaction with alpha-interferon when the two drugs are concurrently administered. | Formal interaction studies have not been performed. |
9.5 Drug-Food Interactions
APO-LAMIVUDINE HBV can be taken with or without food (see 10 Clinical Pharmacology, Absorption).
9.6 Drug-Herb Interactions
Interactions with herbal products have not been established.
9.7 Drug-Laboratory Test Interactions
Interactions with laboratory tests have not been established.
10 CLINICAL PHARMACOLOGY
10.1 Mechanism of Action
Lamivudine is an antiviral agent which is active against hepatitis B virus (HBV) in all cell lines tested and in experimentally infected animals.
10.2 Pharmacodynamics
Lamivudine is metabolised by both infected and uninfected cells to the triphosphate (TP) derivative which is the active form of the parent compound. The intracellular half life of the triphosphate in hepatocytes is 17 to 19 hours in vitro. Lamivudine-TP acts as a substrate for the HBV viral polymerase. The formation of further viral DNA is blocked by incorporation of lamivudine MP into the chain and subsequent chain termination.
Lamivudine-TP is also a substrate for mammalian DNA polymerases, with the subsequent incorporation into mammalian DNA. However, incorporated lamivudine is removed from mammalian DNA by 3'-5' exonuclease DNA repair enzymes. Viral polymerases do not possess such a DNA repair function. Consequently, at concentrations in vitro which inhibit replication of HBV DNA in infected cells, lamivudine has no effect on mammalian mitochondrial DNA synthesis and has no cytotoxicity. In vitro concentrations of lamivudine which cause reductions of mammalian DNA and cytotoxicity are approximately 1000 times or greater than those which inhibit HBV replication. Thus, lamivudine has a high therapeutic index.
10.3 Pharmacokinetics
Absorption
Lamivudine is well absorbed from the gastrointestinal tract, and the bioavailability of oral lamivudine in adults is normally between 80 and 85%. Following oral administration, the mean time (tmax) to maximal serum concentrations (Cmax) is about an hour. At therapeutic dose levels (i.e. 100 mg once daily), Cmax is in the order of 1.1 to 1.5 mcg/mL and trough levels were 0.015 to 0.020 mcg/mL.
Coadministration of lamivudine with food resulted in a delay of tmax and a lower Cmax (decreased by up to 47%). However, the extent (based on the AUC) of lamivudine absorbed was not influenced, therefore lamivudine can be administered with or without food.
Distribution
From intravenous studies, the mean volume of distribution is 1.3 L/kg. Lamivudine exhibits linear pharmacokinetics over the therapeutic dose range and displays low plasma protein binding to albumin.
Limited data shows lamivudine penetrates the central nervous system and reaches the cerebro-spinal fluid (CSF). The mean lamivudine CSF/serum concentration ratio 2 to 4 hours after oral administration was approximately 0.12.
Metabolism
Lamivudine is predominately cleared by renal excretion of unchanged drug. The likelihood of metabolic drug interactions with lamivudine is low due to the small (5 to 10%) extent of hepatic metabolism and the low plasma protein binding.
Elimination
The mean systemic clearance of lamivudine is approximately 0.3 L/h/kg. The observed half life of elimination is 18 to 19 hours. The majority of lamivudine is excreted unchanged in the urine via glomerular filtration and active secretion (organic cationic transport system). The majority of lamivudine (71% ± 16%) is eliminated unchanged in urine within 4 hours following oral administration.
Special Populations and Conditions
- Geriatrics: In elderly patients the pharmacokinetic profile of lamivudine suggests that normal aging with accompanying renal decline has no clinically significant effect on lamivudine exposure, except in patients with creatinine clearance of < 50 mL/min (see 4.2 Recommended Dose and Dosage Adjustment, Renal Insufficiency).
- Pregnancy and Breast-feeding: Following oral administration, lamivudine pharmacokinetics in late-pregnancy were similar to non-pregnant adults. Lamivudine concentrations in infant serum at birth were similar to those in maternal and cord serum at delivery.
- Hepatic Insufficiency: Data obtained in a limited number of patients with significant hepatic impairment, including those with end stage liver disease awaiting transplant, suggest that lamivudine pharmacokinetics are not significantly affected by hepatic dysfunction unless accompanied by renal impairment. Based on pharmacokinetic exposure, it would appear that no dose adjustment is necessary in patients with moderate or severe hepatic impairment.
Renal Insufficiency: Studies in patients with renal impairment show lamivudine elimination is affected by renal dysfunction. Dose reduction in patients with a creatinine
- clearance of < 50 mL/min is necessary, see 4.2 Recommended Dose and Dosage Adjustment, Renal Insufficiency).
11 STORAGE, STABILITY AND DISPOSAL
Store at room temperature 15°C - 30°C. Protect from moisture.
12 SPECIAL HANDLING INSTRUCTIONS
There are no special handling instructions.
PART II: SCIENTIFIC INFORMATION
13 PHARMACEUTICAL INFORMATION
Drug Substance
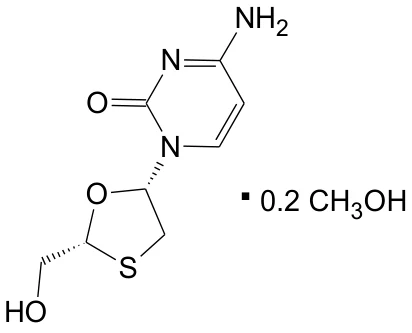
Proper name: Lamivudine methanol solvate
Chemical name: 4-amino-1-[(2R,5S)-2-(hydroxymethyl)-1,3-oxathiolan-5-yl]pyrimidin-2(1H)-one methanol solvate
(2R-cis)- 4-amino-1-[2-(hydroxymethyl)-1,3-oxathiolan-5-yl]-2(1H)-pyrimidinone methanol solvate
(–)-1-[(2R,5S)-2-(hydroxymethyl)-1,3-oxathiolan-5-yl]cytosine
Molecular formula and molecular mass: C8H11N3O3S ∙ 0.2CH4O 235.66 g/mol
Structural Formula:
Physicochemical properties:
Description: Lamivudine methanol solvate is white to off-white powder.
Lamivudine methanol solvate has a melting range of 177° to 178°C and is highly soluble in water. The pKa of the protonated lamivudine was found to be 4.3. The pH of the 1% solution of solvent-free form is 6.9
14 CLINICAL TRIALS
14.1 Clinical Trials by Indication
Trial Design and Study Demographics: Treatment of patients with chronic hepatitis B and evidence of hepatitis B virus (HBV) replication
The safety and efficacy of lamivudine were evaluated in five controlled studies in 856 patients with compensated chronic hepatitis B. Four of the studies were placebo controlled and the fifth (NUCB3010) compared lamivudine to alpha-interferon and to a combination of lamivudine plus alpha-interferon. One of the studies (NUCB3014) was conducted in patients infected with HBV pre-core variants. Patients from NUCB3009 were enrolled into a follow-on study (NUCB3018) where they received up to a further 2 years of therapy. The study designs and results of the comparisons are summarised below (see Table 3):
Table 3 Summary of patient demographics for clinical trials in patients with chronic hepatitis B and evidence of hepatitis B virus (HBV) replication
| Study # | Study design | Dosage, route of administration and duration | Study subjects (n) | Mean age | Sex (% male) |
|---|---|---|---|---|---|
| NUCA3010 | A randomized, double blind comparison of lamivudine 100 mg once daily versus placebo for 52 weeks followed by a 16 week no treatment period in treatment-naïve patients. The primary endpoint was improvement in liver histology. | 100 mg (oral) once daily versus placebo for 52 weeks followed by a 16 week no treatment period in treatment-naïve patients. | 143 | 41 | 83 |
| NUCB3009 | A randomized, double blind comparison of lamivudine 25 mg daily versus lamivudine 100 mg daily versus placebo for 52 weeks in Asian patients. The primary endpoint was improvement in liver histology. | 25 mg (oral) daily versus lamivudine 100 mg (oral) daily versus placebo for 52 weeks | 358 | 31 | 73 |
| NUCB3010 | A randomized, partially blind comparison of | 100 mg (oral) once daily for 52 weeks | 230 | 34 | 74 |
| Study # | Study design | Dosage, route of administration and duration | Study subjects (n) | Mean age | Sex (% male) |
|---|---|---|---|---|---|
| lamivudine 100 mg once daily for 52 weeks versus placebo once daily for 8 weeks followed by placebo once daily plus interferon alpha monotherapy (10MU subcutaneously three times weekly) for 16 weeks versus lamivudine 100 mg once daily for 8 weeks followed by lamivudine 100 mg once daily plus interferon alpha monotherapy (10MU subcutaneously three times weekly) for 16 weeks. The primary endpoint was HBeAg seroconversion with concomitant clearance of HBV DNA. | versus placebo once daily for 8 weeks followed by placebo once daily plus interferon alpha monotherapy (10MU subcutaneously three times weekly) for 16 weeks versus lamivudine 100 mg (oral) once daily for 8 weeks followed by lamivudine 100 mg once daily plus interferon alpha monotherapy (10MU subcutaneously three times weekly) for 16 weeks. | ||||
| NUC3018 | A double blind, placebo controlled follow-on study of NUCB3009; patients were randomised to either 100 mg lamivudine daily, 25 mg lamivudine daily or placebo. The primary endpoint was sustained suppression of HBV DNA. | 100 mg (oral) lamivudine daily, 25 mg (oral) lamivudine daily or placebo. | 334 | 31 | 75 |
| NUCB3014 | A randomized, double blind comparison of lamivudine 100 mg once daily for 52 weeks versus placebo for 26 | Lamivudine 100 mg (oral) once daily for 52 weeks versus placebo for 26 weeks (placebo non-responders were | 125 | 43 | 80 |
| Study # | Study design | Dosage, route of administration and duration | Study subjects (n) | Mean age | Sex (% male) | ||
|---|---|---|---|---|---|---|---|
| weeks (placebo non-responders were withdrawn at week 26) in patients with HBeAg negative (pre-core variant) HBV. The primary endpoint was clearance of HBV DNA and ALT normalization. | withdrawn at week 26) | ||||||
Study Results: Treatment of patients with chronic hepatitis B and evidence of hepatitis B virus (HBV) replication
NUCA3010
After 52 weeks of treatment, a significantly greater number of patients who received lamivudine demonstrated an improvement in necro-inflammatory score compared to placebo (53% Lamivudine vs 24% Placebo; p < 0.001). HBeAg seroconversion occurred significantly more frequently in lamivudine patients (17%) than in placebo treated patients (6%) (p < 0.05). Significantly more lamivudine treated patients demonstrated a sustained HBV DNA response (defined as negative HBV DNA on two consecutive occasions without two consecutive positive values to end week 52) compared to placebo (44 vs 16% respectively; p < 0.001). Similarly, a significantly greater number of lamivudine treated patients (41%) demonstrated a sustained normalization of ALT (defined as two consecutive ALT values < ULN maintained to week 52) compared to placebo (7%; p < 0.001).
NUCB3009
After 52 weeks of treatment a significantly greater number of patients who received lamivudine demonstrated an improvement in necro-inflammatory score compared to placebo (56% Lamivudine vs 25% Placebo; p < 0.001). HBeAg seroconversion occurred significantly more frequently in lamivudine 100 mg patients (16%) than in placebo treated patients (4%) (p < 0.05). Significantly more lamivudine 100 mg treated patients demonstrated a sustained HBV DNA response compared to placebo (57 vs 3% respectively; p < 0.001). Similarly, a significantly greater number of lamivudine 100 mg treated patients (72%) demonstrated a sustained normalization of ALT compared to placebo (24%; p < 0.001).
NUCB3010
There was no statistical difference in the rates of HBeAg seroconversion demonstrated by the three treatment groups (18% lamivudine, 19% interferon-alpha, 29% lamivudine plus interferon alpha). A greater proportion of patients in the lamivudine treated group demonstrated a sustained ALT normalization than in the interferon-alpha alone group (40 vs 17% respectively; p < 0.01) but there was no difference between lamivudine and the combination group.
NUC3018
Fifty-two percent of patients receiving 100 mg of lamivudine daily for two years achieved a sustained suppression in HBV DNA through to week 104 compared to 5% of patients who received lamivudine for one year followed by placebo (p < 0.001). Sustained ALT response was evident in 50% of patients after 104 weeks of 100 mg lamivudine compared to 8% in patients randomised to placebo after the first 52 weeks of lamivudine (p < 0.001).
Patients were maintained on the treatment regimen for one more year (year 3) and were then eligible to enter a 2 year open treatment phase (years 4-5) and receive lamivudine 100 mg daily. A cohort of 280 patients entered this open phase at year four, receiving a total of between 2 and 5 years of lamivudine 100 mg daily therapy during the 5 year trial period. A separate cohort of 58 patients was randomized to lamivudine 100 mg daily from study start and received lamivudine 100 mg daily continuously throughout the five year study period. Patients were then eligible to enter an off-treatment follow-up period of 6 months. In the 58 patients who had received continuous lamivudine therapy (100 mg daily) for 5 years, the HBeAg seroconversion rate (HBeAg loss with HBeAb detection) and ALT normalization rate was 48% and 47% respectively. Elevated baseline ALT levels were a positive predictor of HBeAg seroconversion in this patient population, with 77% of all patients with baseline ALT > 2xULN, 61% of all patients > 1xULN and 18% of all patients with 1xULN seroconverting respectively.
HBeAg seroconversion was observed in some patients with YMDD variant HBV although seroconversion was more frequent in patients without the variant HBV (72% versus 38% respectively). HBeAg seroconversion was maintained in 29 out of 33 (88%) patients followed for 6 months after treatment cessation. The durability of HBeAg seroconversion was similar in patients with the YMDD variant and those without variant HBV virus (91% versus 82% respectively).
NUCB3014
Sustained suppression of HBV DNA at 52 weeks occurred significantly more often in the lamivudine group (71%) than in the placebo group (15%) (p < 0.001) demonstrating that lamivudine is effective at suppressing HBV replication in patients infected with pre-core variant HBV. Sustained normalization of serum ALT occurred in a significantly greater proportion of lamivudine treated patients (67%) compared to placebo (5%).
14.2 Comparative Bioavailability Studies
A randomized, two-way, single-dose, crossover comparative bioavailability study of APO-LAMIVUDINE HBV 100 mg tablets (Apotex Inc.) and Epivir-HBV® 100 mg tablets
(GlaxoSmithKline, USA) was conducted in healthy, adult, male subjects under fasting conditions. Comparative bioavailability data from 24 subjects that were included in the statistical analysis are presented in the following table:
SUMMARY TABLE OF THE COMPARATIVE BIOAVAILABILITY DATA
Lamivudine (1 x 100 mg) Geometric Mean Arithmetic Mean (CV %) | ||||
| Parameter | Test1 | Reference2 | % Ratio of Geometric Means | 90% Confidence Interval |
AUCT (ng·h/mL) | 4910.92 5009.07 (20.16) | 4879.80 4986.07 (21.37) | 100.6 | 95.8 - 105.7 |
AUCI (ng·h/mL) | 5074.57 5173.25 (19.84) | 5050.32 5155.33 (20.81) | 100.5 | 95.8 - 105.4 |
Cmax (ng/mL) | 973.53 1014.27 (30.09) | 1042.12 1083.72 (27.63) | 93.4 | 85.4 - 102.2 |
Tmax3 (h) | 1.00 (0.50 - 3.00) | 1.00 (0.50 - 1.75) | ||
T½4 (h) | 8.64 (11.62) | 8.94 (14.42) | ||
1 APO-LAMIVUDINE HBV (lamivudine as lamivudine methanol solvate) tablets, 100 mg (Apotex Inc.)
2 Epivir-HBV® (lamivudine) tablets, 100 mg (GlaxoSmithKline, USA)
3 Expressed as the median (range) only
4 Expressed as the arithmetic mean (CV%) only
15 MICROBIOLOGY
Antiviral Activity
Lamivudine is a potent inhibitor of extracellular HBV DNA production by HBV-transfected hepatoma cells in vitro. It is also active in animal models of HBV infection, decreasing serum HBV DNA levels in chronically infected chimpanzees, and reducing HBV DNA polymerase activity. Serum levels of HBeAg showed a two-fold decrease in chronically infected chimpanzees treated with lamivudine for 28 days. However, a return in viral production is seen after cessation of treatment in in vitro and in vivo studies. Lamivudine is metabolised intracellularly in hepatocytes to lamivudine 5' triphosphate (lamivudine-TP) which has a long intracellular half life of 17 to 19 hours. Its main mode of action is by incorporation of lamivudine monophosphate into the growing viral DNA chain, resulting in chain termination.
Cytotoxicity and Selectivity
Lamivudine-TP is a more potent inhibitor of viral DNA polymerization than it is of mammalian DNA polymerisation. In addition, although lamivudine-TP is a substrate for host DNA polymerase γ, and is incorporated into DNA, the product is also a substrate for the 3' 5' exonuclease activity of mitochondrial DNA polymerase γ. Consequently, lamivudine does not act as a chain terminator of mitochondrial DNA synthesis, has little effect on mammalian cell mitochondrial DNA content and does not interfere with normal cellular deoxynucleotide metabolism. These data suggest that lamivudine has a low potential to cause mitochondrial toxicity. Furthermore, lamivudine has a low cytotoxicity to a range of cell types in vitro, including bone marrow progenitor cells. The lack of mitochondrial or cellular toxicity gives lamivudine a high therapeutic index. The specificity of lamivudine for HBV is demonstrated by its lack of activity against a number of RNA and DNA viruses (except for HIV), and other micro organisms including bacteria and fungi. These data demonstrate lamivudine is a specific, potent, inhibitor of HBV.
Resistance
Reduced sensitivity of HBV to lamivudine is conferred by mutations resulting in amino acid changes in the YMDD region of the catalytic domain of HBV polymerase. Two key mutations identified are methionine 552 to valine plus leucine 528 to methionine, or methionine 552 to isoleucine.
In the Phase III studies HBV YMDD variants have been detected with a frequency of 16 to 32% following one year of treatment with lamivudine. The incidence of YMDD variant HBV increases with duration of treatment (42% at two years, 53% after 3 years, 69% after 4 years, 59% after 5 years - NUCB3018 and may be higher in immunocompromised patients). Although better treatment response was seen compared to placebo, YMDD variants were associated with evidence of diminished treatment response at 52 weeks relative to lamivudine treated patients without evidence of YMDD variants.
In the population of patients with HBV YMDD variants, patients generally continued to show lower HBV DNA and ALT levels than pretreatment values, even after variants were detectable for 52 weeks or longer. In addition, seroconversion rates in patients with YMDD variants were similar to placebo. Given the risk of YMDD mutant HBV, maintenance of lamivudine monotherapy is not appropriate in patients with detectable serum HBV DNA at or beyond 24 weeks of treatment.
16 NON-CLINICAL TOXICOLOGY
Acute Toxicity: Acute toxicity studies have been performed in the mouse and rat. The acute oral administration of very high doses of lamivudine (two doses of 2000 mg/kg) in mice was associated with transient increases in sexual activity in males and general activity in males and females. There were no deaths and no evidence of target organ toxicity. Therefore the maximum non-lethal oral dose of lamivudine in mice is greater than two doses of 2000 mg/kg.
The acute intravenous administration of lamivudine at 2000 mg/kg was well tolerated by both mice and rats and was not associated with any target organ toxicity. A number of non-specific clinical signs were observed which were more severe in rats but were all of relatively short duration.
Long Term Toxicity: In repeat dose toxicity studies, lamivudine was very well tolerated in the rat at oral doses up to 2000 mg/kg b.i.d. for 6 months. Treatment related effects were restricted to minor hematological (mainly red cell parameters), clinical chemistry and urinalysis changes, and the mucosal hyperplasia of the cecum (in the 6 month study). The no (toxicologically important) effect level was 450 mg/kg b.i.d.
In the dog, oral doses of 1500 mg/kg b.i.d. in males and 1000 mg/kg b.i.d. in females for a period of 12 months were well tolerated. Treatment related changes included reductions in red cell counts at all dose levels, associated with increased MCV and MCH, and reductions in total leucocyte, neutrophil and lymphocyte counts in high dose animals, but with no effect on bone marrow cytology. Deaths were seen in females dosed with 1500 mg/kg b.i.d. in a 3 month study but not in a 12 month study, using a dose of 1000 mg/kg b.i.d.
When administered orally for one month, at a dose of 1000 mg/kg b.i.d., lamivudine demonstrated low hematotoxic potential in the mouse, and did not significantly enhance the hematotoxicity of zidovudine or interferon alpha.
Carcinogenicity and Genotoxicity: Lamivudine long term carcinogenicity studies in mice and rats showed no evidence of carcinogenic potential at exposures up to 34 times (mice) and 200 times (rats) based on AUC observed in humans at the recommended therapeutic dose.
Traditional 24 month carcinogenicity studies using lamivudine have been conducted in mice and rats at exposures up to 10 times (mice) and 58 times (rats) those observed in humans at recommended therapeutic doses. The following results should be noted. In mice, there appeared to be an increased incidence of histiocytic sarcoma in female mice treated with 180 mg/kg/day (6 of 60 mice) and 2000 mg/kg/day (5 of 60 mice) when compared to control mice (two control groups with 1 of 60 and 2 of 60 mice). There did not appear to be an increased incidence in histiocytic sarcoma in females mice treated with 600 mg/kg/day (3 of 60 mice). It should be noted that the control incidence of this type of tumour in this strain of mice can be as high as 10%, similar to that found in the 180 and 2000 mg/kg/day groups. In rats, there appeared to be an increased incidence of endometrial epithelial tumours in female rats treated with 3000 mg/kg/day (5 of 55 rats) when compared to control rats (two control groups each with 2 of 55 rats). There did not appear to be an increased incidence for endometrial tumours in rats treated with 1000 mg/kg/day (2 of 55 rats) or 300 mg/kg/day (1 of 55 rats). It should be noted that there did not appear to be an increased incidence of any proliferative non-neoplastic epithelial lesions in treated female rats when compared to control rats, and the incidence of adenocarcinoma (5/55 or 9%) was only slightly higher than recorded controls at the laboratory where the study was conducted (4/50 or 8%). The statistical significance of the findings in mice and rats varied with the statistical analysis conducted, and therefore, the statistical and hence, the clinical significance of these findings are uncertain.
However, based on the similarity to historical control data, it was concluded that the results of long term carcinogenicity studies in mice and rats for lamivudine did not seem to show a carcinogenic potential relevant for humans.
Lamivudine was not active in a microbial mutagenicity screen or an in vitro cell transformation assay, but showed weak in vitro mutagenic activity in a cytogenetic assay using cultured human lymphocytes and in the mouse lymphoma assay. However, lamivudine showed no evidence of in vivo genotoxic activity in the rat at oral doses of up to 4,000 mg/kg per day (30-40 times higher than the anticipated clinical plasma levels).
Reproductive and Developmental Toxicology: A range of studies has been performed to assess the effects of repeated oral administration of lamivudine upon mammalian reproduction and development. In a rat fertility study, except for a few minor changes in high dose (2000 mg/kg b.i.d) animals, the overall reproductive performance of the F0 and F1 generation animals, and the development of the F1 and F2 generation, was unaffected by treatment with lamivudine.
Lamivudine was not teratogenic in the rat or rabbit, at doses up to 2000 mg/kg b.i.d. and 500 mg/kg b.i.d., respectively. In the rabbit a slight increase in the incidence of pre-implantation loss at doses 20 mg/kg b.i.d. and above indicates a possible early embryolethal effect. There was no such effect in the rat. These marginal effects occurred at relatively low doses, which produced plasma levels comparable to those achieved in patients.
In a peri-/post-natal/juvenile toxicity study in rats, some histological inflammatory changes at the ano-rectal junction and slight diffuse epithelial hyperplasia of the cecum were observed in dams and pups at the high dose level. An increased incidence of urination upon handling was also seen in some offspring receiving 450 or 2000 mg/kg. In addition, a reduction in testes weight was observed in juvenile males at 2000 mg/kg which was associated with slight to moderate dilatation of the seminiferous tubules.
Reproductive studies in animals have not shown evidence of teratogenicity, and showed no effect on male or female fertility. Lamivudine induced early embryolethality when administered to pregnant rabbits, at exposure levels comparable to those achieved in humans. Consistent with passive transmission of the drug across the placenta, lamivudine concentrations in infant serum at birth were similar to those in maternal and cord serum. However, there was no evidence of embryonic loss in rats at exposure levels of approximately 60 times the clinical exposure (based on Cmax).
17 SUPPORTING PRODUCT MONOGRAPHS
- 1. Heptovir® lamivudine tablets 100 mg, submission control 254986, Product Monograph, GlaxoSmithKline Inc. (DEC 17, 2021).