


Product Monograph - Apo-Lamotrigine
RECENT MAJOR LABEL CHANGES
| 4 DOSAGE AND ADMINISTRATION, 4.2 Recommended Dose and Dosage Adjustment | 06/2025 |
|---|---|
| 7 WARNINGS AND PRECAUTIONS, General | 06/2025 |
| 7 WARNINGS AND PRECAUTIONS, Skin, Asian Ancestry and Allelic variation in HLA-B | 06/2025 |
TABLE OF CONTENTS
Sections or subsections that are not applicable at the time of authorization are not listed.
RECENT MAJOR LABEL CHANGES ........................................................................................... 2
TABLE OF CONTENTS ............................................................................................................. 2
PART I: HEALTH PROFESSIONAL INFORMATION ..................................................................... 4
1 INDICATIONS ............................................................................................................... 4
1.1 Pediatrics ................................................................................................................... 4
1.2 Geriatrics .................................................................................................................... 4
2 CONTRAINDICATIONS .................................................................................................. 4
3 SERIOUS WARNINGS AND PRECAUTIONS BOX .............................................................. 4
4 DOSAGE AND ADMINISTRATION .................................................................................. 5
4.1 Dosing Considerations ............................................................................................... 5
4.2 Recommended Dose and Dosage Adjustment .......................................................... 6
4.4 Administration ......................................................................................................... 13
4.5 Missed Dose ............................................................................................................. 13
5 OVERDOSAGE ............................................................................................................ 13
6 DOSAGE FORMS, STRENGTHS, COMPOSITION AND PACKAGING ................................. 14
7 WARNINGS AND PRECAUTIONS .................................................................................. 15
7.1 Special Populations .................................................................................................. 24
7.1.1 Pregnant Women ..................................................................................................... 24
7.1.2 Breast-feeding ......................................................................................................... 26
7.1.4 Geriatrics .................................................................................................................. 26
8 ADVERSE REACTIONS ................................................................................................. 27
8.1 Adverse Reaction Overview ..................................................................................... 27
8.2 Clinical Trial Adverse Reactions ............................................................................... 27
8.3 Less Common Clinical Trial Adverse Reactions ....................................................... 33
8.5 Post-Market Adverse Reactions .............................................................................. 33
9 DRUG INTERACTIONS ................................................................................................. 35
9.2 Drug Interactions Overview ..................................................................................... 35
9.3 Drug-Behavioural Interactions ................................................................................ 35
9.4 Drug-Drug Interactions ............................................................................................ 35
9.6 Drug-Herb Interactions ............................................................................................ 41
9.7 Drug-Laboratory Test Interactions .......................................................................... 41
10 CLINICAL PHARMACOLOGY......................................................................................... 42
10.1 Mechanism of Action ............................................................................................... 42
10.2 Pharmacodynamics .................................................................................................. 42
10.3 Pharmacokinetics..................................................................................................... 42
11 STORAGE, STABILITY AND DISPOSAL ........................................................................... 46
12 SPECIAL HANDLING INSTRUCTIONS ............................................................................ 46
PART II: SCIENTIFIC INFORMATION ...................................................................................... 47
13 PHARMACEUTICAL INFORMATION ............................................................................. 47
14 CLINICAL TRIALS ......................................................................................................... 47
14.2 Study Results ........................................................................................................... 47
14.3 Comparative Bioavailability Studies ........................................................................ 48
15 MICROBIOLOGY ......................................................................................................... 49
16 NON-CLINICAL TOXICOLOGY ....................................................................................... 49
17 SUPPORTING PRODUCT MONOGRAPHS ..................................................................... 53
PATIENT MEDICATION INFORMATION ................................................................................. 54
PART I: HEALTH PROFESSIONAL INFORMATION
1 INDICATIONS
Adults (≥ 18 years of age)
APO-LAMOTRIGINE (lamotrigine) is indicated:
- as adjunctive therapy for the management of epilepsy not satisfactorily controlled by conventional therapy;
- for use as monotherapy following withdrawal of concomitant antiepileptic drugs;
- as adjunctive therapy for the management of the seizures associated with Lennox-Gastaut syndrome.
1.1 Pediatrics
Pediatrics (<18 years of age)
APO-LAMOTRIGINE (lamotrigine) is indicated as adjunctive therapy for the management of the seizures associated with Lennox-Gastaut syndrome. APO-LAMOTRIGINE is not recommended in children weighing less than 9 kg (see 4 DOSAGE AND ADMINISTRATION) and treatment should only be initiated in children weighing 42 kg and above (see 4 DOSAGE AND ADMINISTRATION, Pediatric Dosing with Lamotrigine for Patients Receiving Medications that Induce Lamotrigine Glucuronidation, without Valproic-Acid).
Safety and efficacy in patients below the age of 16 years, other than those with Lennox-Gastaut Syndrome, have not been established.
1.2 Geriatrics
Geriatrics (> 65 years of age): No dosage adjustment is required in patients over 65 years of age.
2 CONTRAINDICATIONS
Patients who are hypersensitive to this drug or to any ingredient in the formulation or component of the container. For a complete listing, see 6 DOSAGE FORMS, STRENGTHS, COMPOSITION AND PACKAGING.
3 SERIOUS WARNINGS AND PRECAUTIONS BOX
Serious Warnings and Precautions
Serious skin rashes
- Serious and sometimes fatal skin rashes, including Stevens-Johnson Syndrome (SJS) and Toxic Epidermal Necrolysis (TEN), have occurred with the use of lamotrigine. The incidence of these rashes in clinical trials was 1% (1/100) in pediatric patients (age < 16 years) and 0.3% (3/1000) in adults.
- In children, the initial presentation of a rash can be mistaken for an infection. Physicians should consider the possibility of a drug reaction in children that develop symptoms of rash and fever during the first eight weeks of therapy.
- Risk of rapid titration: Do not exceed the recommended initial dose and subsequent dose escalations of APO-LAMOTRIGINE. A higher incidence of serious skin rashes (see 7 WARNINGS AND PRECAUTIONS, Skin-related events, Table 7 and Table 8; see also 4 DOSAGE AND ADMINISTRATION) has been associated with more rapid initial titration (exceeding the recommended initial dose or exceeding the recommended dose escalation).
- Risk of concomitant use with valproic acid.
- Risk with history of rash to other antiepileptics: In two studies (n = 767 and n = 988), the frequency of rash with lamotrigine treatment was approximately 3 to 4 times higher in patients with a history of allergy or rash to other anti-epileptics, compared to those without such history.
- Nearly all cases of rash associated with lamotrigine have occurred within 2 to 8 weeks of treatment initiation. However, isolated cases have been reported after prolonged treatment (e.g., 6 months). Accordingly, duration of therapy cannot be relied upon as a means to predict the potential risk signalled by the first appearance of a rash.
- Although benign rashes also occur with lamotrigine, it is not possible to predict reliably which rashes will prove to be life threatening. Accordingly, all patients who develop rash should be promptly evaluated and APO-LAMOTRIGINE withdrawn immediately, unless the rash is clearly not drug related.
4 DOSAGE AND ADMINISTRATION
4.1 Dosing Considerations
Potential for Serious Dermatological Reactions
Do not exceed the recommended initial dose and subsequent dose escalations of APO-LAMOTRIGINE. More rapid initial titration has been associated with an increased incidence of serious dermatological reactions (see 3 SERIOUS WARNINGS AND PRECAUTIONS BOX), as has concomitant use of valproic acid, particularly in the absence of AEDs that induce lamotrigine glucuronidation (see 9 DRUG INTERACTIONS). Patients with a history of rash or allergy to other AEDS are more at risk for lamotrigine-associated rash than those without such history (see 7 WARNINGS AND PRECAUTIONS).
Restarting APO-LAMOTRIGINE Therapy
It is recommended that APO-LAMOTRIGINE not be restarted in patients who discontinued due to rash associated with prior treatment with APO-LAMOTRIGINE unless the potential benefits clearly outweigh the risks. If the decision is made to restart a patient who has discontinued APO-LAMOTRIGINE for any reason, the need to restart with the initial dosing recommendations should be assessed. The greater the interval of time since the previous dose, the greater consideration should be given to restarting with the initial dosing recommendations. If a patient has discontinued APO-LAMOTRIGINE for a period of more than 5 half-lives, it is recommended that initial dosing recommendations and guidelines be followed. The half-life of APO-LAMOTRIGINE is affected by other concomitant medications (see 10 CLINICAL PHARMACOLOGY).
Withdrawal of Concomitant AEDs in Adults
Concomitant AEDs may be decreased over a 5-week period, by approximately 20% of the original dose every week. However, a slower taper may be used if clinically indicated. During this period, the dose of APO-LAMOTRIGINE administered will be dependent upon the effect of the drug being withdrawn on the pharmacokinetics of lamotrigine, together with the overall clinical response of the patient. The withdrawal of enzyme inducing AEDs (i.e., phenytoin, phenobarbital, primidone, and carbamazepine) will result in an approximate doubling of the t½ of lamotrigine. Under these conditions, it may be necessary to reduce the dose of APO-LAMOTRIGINE. In contrast, the withdrawal of enzyme inhibiting AEDs (i.e., valproic acid) will result in a decrease in the t½ of lamotrigine and may require an increase in the dose of APO-LAMOTRIGINE.
4.2 Recommended Dose and Dosage Adjustment
APO-LAMOTRIGINE should be added to the patient's current antiepileptic therapy.
Valproic acid more than doubles the elimination half-life of lamotrigine and reduces the plasma clearance by 50%; conversely, drugs that induce lamotrigine glucuronidation such as carbamazepine, phenytoin, phenobarbital, and primidone reduce the elimination half-life of lamotrigine by 50% and double the plasma clearance (see 10 CLINICAL PHARMACOLOGY). These clinically important interactions require dosage schedules of APO-LAMOTRIGINE as summarized in Table 1 through Table 3.
APO-LAMOTRIGINE does not alter plasma concentrations of concomitantly administered AEDs that induce lamotrigine glucuronidation and therefore they do not usually require dose adjustment to maintain therapeutic plasma concentrations. For patients receiving APO-LAMOTRIGINE in combination with other AEDs, an evaluation of all AEDs in the regimen should be considered if a change in seizure control or an appearance or worsening of adverse experiences is observed. If there is a need to discontinue therapy with APO-LAMOTRIGINE, a step-wise reduction of dose over at least two weeks (approximately 50% per week) is recommended unless safety concerns (i.e. rash) require a more rapid withdrawal (see 7 WARNINGS AND PRECAUTIONS).
The relationship of plasma concentration to clinical response has not been established for lamotrigine. Dosing of APO-LAMOTRIGINE should be based on therapeutic response. In controlled clinical studies, doses of lamotrigine that were efficacious generally produced steady-state trough plasma lamotrigine concentrations of 1 to 4 mcg/mL in patients receiving one or more concomitant AEDs. Doses of lamotrigine producing this plasma concentration range were well tolerated. As with any antiepileptic drug, the oral dose of APO-LAMOTRIGINE should be adjusted to the needs of the individual patient, taking into consideration the concomitant AED therapy the patient is receiving.
Adults and Children Over 12 Years of Age
For patients taking AEDs whose pharmacokinetic interactions with APO-LAMOTRIGINE are currently unknown, follow the titration schedule for concomitant VPA (regardless of any concomitant medication).
Table 1 Escalation regimen for APO-LAMOTRIGINE in Patients over 12 Years of Age
| Patients Taking Medications that induce lamotrigine glucuronidation1 | Patients Taking Medications that neither induce nor inhibit lamotrigine glucuronidation2 | ||||||||
| with valproate3 | without valproate3 | ||||||||
| Weeks 1 and 2 | 25 mg once a day | 50 mg once a day | 25 mg once a day | ||||||
| Weeks 3 and 4 | 25 mg twice a day | 50 mg twice a day | 25 mg twice a day | ||||||
| Weeks 5 onwards to maintenance | Increase by 25-50 mg every 1 to 2 weeks | Increase by 100 mg every 1 to 2 weeks | Increase by 25-50 mg every 1 to 2 weeks | ||||||
| Usual Maintenance Dose | 50-100 mg twice a day | 150-250 mg twice a day | 50-100 mg twice a day | ||||||
1 Medications that induce lamotrigine glucuronidation include carbamazepine, phenobarbital, phenytoin, primidone, rifampin, lopinavir/ritonavir and atazanavir/ritonavir
2 Medications that neither inhibit nor induce lamotrigine glucuronidation include olanzapine, oxcarbazepine, felbamate, gabapentin, levetiracetam, pregabalin, topiramate and zonisamide
3 Valproic acid is an inhibitor of lamotrigine glucuronidation
For patients taking valproic acid regardless of any concomitant medication, a more cautious titration schedule is available than that detailed in Table 1. During weeks 1 and 2, a dose of 25 mg every other day may be given instead of 25 mg once daily dose. During weeks 3 and 4, a dose of 25 mg once a day may be given instead of the 25 mg twice daily dose (total daily dose of 50 mg).
There have been no controlled studies to establish the effectiveness or optimal dosing regimen of add-on lamotrigine therapy in patients receiving only AEDs that neither inhibit nor induce lamotrigine glucuronidation or valproic acid. However, available data from open clinical trials indicate that the addition of lamotrigine under these conditions is associated with a higher incidence of serious rash or rash-related withdrawal, even at an initial titration dose of 12.5 mg daily (see 7 WARNINGS AND PRECAUTIONS, Skin-related events, Table 7 and Table 8).
The potential medical benefits of the addition of APO-LAMOTRIGINE under these conditions must be weighed against the increased risk of serious rash. If use of APO-LAMOTRIGINE under these conditions is considered clinically indicated, titration should proceed with extreme caution, especially during the first six weeks of treatment.
Starting APO-LAMOTRIGINE in Women Taking Oral Contraceptives:
Although oral contraceptives have been shown to increase the clearance of lamotrigine (see 9.4 Drug-Drug Interactions, Oral Contraceptives), no adjustments to the recommended dose escalation guidelines for APO-LAMOTRIGINE should be necessary solely based on the use of oral contraceptives. Therefore, dose escalation should follow the recommended guidelines based on whether APO-LAMOTRIGINE is added to valproate (an inhibitor of lamotrigine glucuronidation) or an inducer of lamotrigine glucuronidation, or whether APO-LAMOTRIGINE is added in the absence of valproate or an inducer of lamotrigine glucuronidation.
Adjustments to the Maintenance Dose of APO-LAMOTRIGINE:
Taking or Starting Oral Contraceptives: For women not taking inducers of lamotrigine glucuronidation (including carbamazepine, phenytoin, phenobarbital, primidone, or rifampin), the maintenance dose of APO-LAMOTRIGINE will in most cases need to be increased, by as much as 2-fold over the recommended target maintenance dose (see 9.4 Drug-Drug Interactions, Oral Contraceptives). It is recommended that from the time that the hormonal contraceptive is started, the APO-LAMOTRIGINE dose is increased by 50 to 100 mg/day every week, according to the individual clinical response. Dose increases should not exceed this rate, unless the clinical response supports larger increases. Gradual transient increases in lamotrigine levels may occur during the week of no active hormone preparation (pill-free week), as much as 2-fold at the end of the week, and these increases will be greater if the dose of APO-LAMOTRIGINE is increased in the few days before or during the pill-free week (see 9.4 Drug-Drug Interactions, Oral Contraceptives and 7 WARNINGS AND PRECAUTIONS, General, Estrogen-containing Products Including Hormonal Contraceptives).
Stopping Oral Contraceptives: For women not taking inducers of lamotrigine glucuronidation (e.g., carbamazepine, phenytoin, phenobarbital, primidone, or rifampin), the maintenance dose of APO-LAMOTRIGINE will in most cases need to be to be decreased by as much as 50% of the maintenance dose with concurrent oral contraceptives, (see 9.4 Drug-Drug Interactions, Oral Contraceptives). It is recommended to gradually decrease the daily dose of APO-LAMOTRIGINE by 50 to 100 mg each week (at a rate not exceeding 25% of the total daily dose per week) over a period of 3 weeks, unless the clinical response indicates otherwise.
Women and Other Hormonal Contraceptive Preparations or Hormone Replacement Therapy:
Although the effect of other estrogen-containing therapies, such as hormone replacement therapies (HRTs) on the pharmacokinetics of lamotrigine has not been evaluated, the effect may be similar to oral contraceptives (see 9.4 Drug-Drug Interactions, Oral Contraceptives). Therefore, close clinical monitoring and similar adjustments to the dosage of APO-LAMOTRIGINE may be needed (see 7 WARNINGS AND PRECAUTIONS, General, Estrogen-containing Products Including Hormonal Contraceptives and 9.4 Drug-Drug Interactions, Oral Contraceptives, Interactions with Other Hormonal Contraceptives or Hormone Replacement Therapy).
Pediatrics
Safety and efficacy in patients below the age of 16 years, other than those with Lennox-Gastaut Syndrome, have not been established. Treatment of children with APO-LAMOTRIGINE should only be initiated in those weighing 42 kg and above.
The starting doses and dose escalations listed below are different than those used in clinical trials, however the maintenance doses are the same as those used in clinical trials. Smaller starting doses and slower dose escalations than those used in clinical trials are recommended because of concern that the risk of serious rash may be greater with higher initial doses and more rapid dose escalation. Consequently, it may take several weeks to months to achieve an individualized maintenance dose.
To ensure a therapeutic dose is maintained, the weight of a child must be monitored and the dose reviewed as weight changes occur.
Recommended doses have been determined based on the individual tablet strengths which most closely approximates, but does NOT exceed, the target dose calculated on the basis of patient weight. APO-LAMOTRIGINE should not be administered if the calculated daily dose is less than 1 mg (e.g., patients weighing less than 9 kg [20 lbs]).
For patients taking AEDs whose pharmacokinetic interactions with APO-LAMOTRIGINE are currently unknown, follow the titration schedule for concomitant VPA.
Table 2 Pediatric Dosing with Lamotrigine for Patients Receiving Valproic Acid, Regardless of any other Concomitant Medication
| Weight Range | Weeks 1 + 2 0.15 mg/kg once a day | Weeks 3 + 4 0.3 mg/kg once a day | Weeks 5 and onwards to Usual Maintenance Dose1 To achieve maintenance, doses may be increased by 0.3 mg/kg every 1-2 weeks, to a maximum of 200 mg/day. Usual maintenance dose is between 1-5 mg/kg once a day, as one dose or two divided doses | |
| < 9 kg | < 20 lbs | Do not take lamotrigine since there is insufficient experience in children weighing less than 9 kg | ||
| 9-13 kg | 20-29 lbs | 2 mg every other day | 2 mg/day | Increase dose by no more than 2 mg/day every 1-2 weeks |
| 14-16 kg | 31-35 lbs | 2 mg/day | 4 mg/day | Increase dose by no more than 4 mg/day every 1-2 weeks |
| 17-33 kg | 37-73 lbs | 5 mg every other day | 5 mg/day | Increase dose by no more than 5 mg/day every 1-2 weeks |
| 34-49 kg | 75-108 lbs | 5 mg/day | 10 mg/day | Increase dose by no more than 10 mg/day every 1-2 weeks |
| ≥ 50 kg2 | ≥ 110 lbs | 5 mg/day | 15 mg/day | Increase dose by no more than 15 mg/day every 1-2 weeks |
1 It may take several weeks to months to achieve an individualized maintenance dose
2 Insufficient data are available to be able to support the mg/kg dosing in patients weighing more than 50 kg
Table 3 Pediatric Dosing with Lamotrigine for Patients Receiving Medications that Induce Lamotrigine Glucuronidation1,2,*, without Valproic-Acid
| Weight Range | Weeks 1 + 2 0.3 mg/kg twice a day | Weeks 3 + 4 0.6 mg/kg twice a day | Week 5 and onwards to Usual Maintenance Dose3 To achieve maintenance, doses may be increased by 1.2 mg/kg every 1-2 weeks, to a maximum of 400 mg/day. Usual maintenance dose is between 2.5 - 7.5 mg/kg twice a day | |
| Weight Range | Weeks 1 + 2 0.3 mg/kg twice a day | Weeks 3 + 4 0.6 mg/kg twice a day | Week 5 and onwards to Usual Maintenance Dose3 To achieve maintenance, doses may be increased by 1.2 mg/kg every 1-2 weeks, to a maximum of 400 mg/day. Usual maintenance dose is between 2.5 - 7.5 mg/kg twice a day | |
| < 9 kg | < 20 lbs | Do not take lamotrigine since there is insufficient experience in children weighing less than 9 kg | ||
| 9-12 kg | 20-26 lbs | 5 mg/day | 10 mg/day | Increase dose by no more than 10 mg/day every 1-2 weeks |
| 13-16 kg | 29-35 lbs | 5 mg/day | 15 mg/day | Increase dose by no more than 15 mg/day every 1-2 weeks |
| 17-20 kg | 37-44 lbs | 10 mg/day | 20 mg/day | Increase dose by no more than 20 mg/day every 1-2 weeks |
| 21-24 kg | 46-53 lbs | 10 mg/day | 25 mg/day | Increase dose by no more than 25 mg/day every 1-2 weeks |
| 25-29 kg | 55-64 lbs | 15 mg/day | 30 mg/day | Increase dose by no more than 30 mg/day every 1-2 weeks |
| 30-33 kg | 66-73 lbs | 15 mg/day | 35 mg/day | Increase dose by no more than 35 mg/day every 1-2 weeks |
| 34-37 kg | 75-81 lbs | 20 mg/day | 40 mg/day | Increase dose by no more than 40 mg/day every 1-2 weeks |
| 38-41 kg | 84-90 lbs | 20 mg/day | 45 mg/day | Increase dose by no more than 45 mg/day every 1-2 weeks |
| 42-45 kg | 92-99 lbs | 25 mg/day | 50 mg/day | Increase dose by no more than 50 mg/day every 1-2 weeks |
| 46-49 kg | 101-108 lbs | 25 mg/day | 55 mg/day | Increase dose by no more than 55 mg/day every 1-2 weeks |
| 50-54 kg | 110-119 lbs | 30 mg/day | 60 mg/day | Increase dose by no more than 60 mg/day every 1-2 weeks |
| 55-58 kg | 121-128 lbs | 30 mg/day | 65 mg/day | Increase dose by no more than 65 mg/day every 1-2 weeks |
| ≥ 59 kg4 | ≥ 130 lbs | 35 mg/day | 70 mg/day | Increase dose by no more than 70 mg/day every 1-2 weeks |
1 Medications that induce lamotrigine glucuronidation include carbamazepine, phenobarbital, phenytoin, primidone, rifampin, lopinavir/ritonavir and atazanavir/ritonavir
2 Can be given as two divided doses
3 It may take several weeks to months to achieve an individualized maintenance dose
4 Insufficient data are available to be able to support the mg/kg dosing in patients weighing more than 59 kg.
* Total daily dose can be divided
Geriatrics
No dosage adjustment from the recommended adult schedule is required. The pharmacokinetics of lamotrigine in this age group do not differ significantly from a non-elderly population (see also 10 CLINICAL PHARMACOLOGY and 8.2 Clinical Trial Adverse Reactions).
Renal Insufficiency
The elimination half-life of lamotrigine is prolonged in patients with impaired renal function (see 10 CLINICAL PHARMACOLOGY). Caution should be exercised in dose selection for patients with impaired renal function.
Hepatic Insufficiency
Mild and Moderate Hepatic Insufficiency: It is recommended that initial, escalation and maintenance doses be reduced by approximately 50% in patients with either mild or moderate (Child-Pugh Grade A or B) hepatic impairment; dosage schedules based on pharmacokinetic data are summarized in Table 4. Maintenance doses may be adjusted according to clinical response and tolerance (see also 10 CLINICAL PHARMACOLOGY and 7 WARNINGS AND PRECAUTIONS).
Table 4 Dosing for Mild (Child-Pugh Grade A) and Moderate (Child-Pugh Grade B) Hepatic-Impaired Adult Patients (Based on pharmacokinetic data from 12 mild and 5 moderate hepatic-impaired subjects given a single 100 mg dose)
| Weeks 1 + 2 | Weeks 3 + 43 | Week 5 and onwards to Usual Maintenance Dose2 | |
| Lamotrigine + EI AEDS1 | 25 mg/day | 50 mg/day | To achieve maintenance, doses may be increased by 50 mg every 1 to 2 weeks. |
| Lamotrigine + EI AEDS + VPA | 10 mg/day | 20 mg/day | To achieve maintenance, doses may be increased by 10-20 mg every 1 to 2 weeks. |
| Lamotrigine + VPA* (± non-EI AEDS) | 5 mg/day | 10 mg/day | To achieve maintenance, doses may be increased by 10-20 mg every 1 to 2 weeks. |
1 AEDs that induce lamotrigine glucuronidation include carbamazepine, phenobarbital, phenytoin, and primidone
2 It may take several weeks to months to achieve an individualized maintenance dose
3 Can be given as two divided doses
* Based on dosage recommendations from the United Kingdom
Severe Hepatic Insufficiency: Caution should be exercised with severe hepatic impaired patients with epilepsy, as there is no clinical experience with lamotrigine in this group. It is recommended that initial, escalation and maintenance doses be reduced by approximately 75% in severe (Child-Pugh Grade C) hepatic impairment; dosage schedules based on pharmacokinetic data are summarized in Table 5. Maintenance doses may be adjusted according to clinical response and (see also 10 CLINICAL PHARMACOLOGY and 7 WARNINGS AND PRECAUTIONS).
Table 5 Dosing for Severe (Child-Pugh Grade C) Hepatic-Impaired Adult Patients (Based on pharmacokinetic data from 7 severe hepatic-impaired subjects given a single 100 mg dose)
| Weeks 1 + 2 | Weeks 3 + 43 | Week 5 and onwards to Usual Maintenance Dose2 | |
| Lamotrigine + EI AEDS1 | 10 mg/day | 20 mg/day | To achieve maintenance, doses may be increased by 20 mg every 1 to 2 weeks. |
| Lamotrigine + EI AEDS + VPA | 5 mg/day | 10 mg/day | To achieve maintenance, doses may be increased by 5-10 mg every 1 to 2 weeks. |
| Lamotrigine + VPA* (± non-EI AEDS) | 5 mg every other day | 5 mg/day | To achieve maintenance, doses may be increased by 5-10 mg every 1 to 2 weeks. |
1 AEDs that induce lamotrigine glucuronidation include carbamazepine, phenobarbital, phenytoin, and primidone
2 It may take several weeks to months to achieve an individualized maintenance dose
3 Can be given as two divided doses * Based on dosage recommendations from the United Kingdom
4.4 Administration
APO-LAMOTRIGINE (lamotrigine) is intended for oral administration and may be taken with or without food. APO-LAMOTRIGINE tablets should be swallowed whole and should not be chewed or crushed.
4.5 Missed Dose
If a dose is missed, the patient should be instructed to take the next dose as soon as they remember unless the next dose is due in less than 4 hours, in which case they should skip the missed dose and take the next dose when it is due. The patient should be instructed to not make up for a missed dose by taking a double dose next time.
5 OVERDOSAGE
Adults
Acute overdoses involving quantities up to 15 g have been reported for lamotrigine, some of which have been fatal. In general, overdose has resulted in symptoms including nystagmus, ataxia, grand mal convulsions, impaired consciousness coma and intraventricular conduction delay (QRS broadening).
Pediatrics
Among patients ≤ 16 years of age, reports of single doses of lamotrigine have included ingestion of 3 g by a 14 year old female and approximately 1 g by a 4 year old male. The 14 year old female was taking marketed lamotrigine; after the dose, she lost consciousness and was admitted to the hospital for supportive therapy, where she recovered fully (time to recovery not reported). The 4 year old male was drowsy and agitated when found, and his condition worsened to coma level II after hospitalization. He was given supportive therapy, and his condition improved rapidly with full recovery in 3 days.
There are no specific antidotes for APO-LAMOTRIGINE. Following a suspected overdose, immediate hospitalization of the patient is advised. In the event of a very recent overdose/ingestion of a potentially life-threatening amount of the drug, emesis may be induced if indicated. General supportive care is indicated, including frequent monitoring of vital signs and close observation of the patient. It is uncertain whether hemodialysis is an effective means of removing lamotrigine from the blood. In six renal failure patients, about 20% of the amount of lamotrigine in the body was removed during 4 hours of hemodialysis.
For management of a suspected drug overdose, contact your regional poison control centre.
6 DOSAGE FORMS, STRENGTHS, COMPOSITION AND PACKAGING
Table 6 Dosage Forms, Strengths, Composition
| Route of Administration | Dosage Form / Strength / Composition | Non-medicinal Ingredients |
|---|---|---|
| Oral | Tablets 25 mg, 100 mg and 150 mg | Colloidal silicon dioxide, ferric oxide yellow (150 mg tablets only), magnesium stearate, microcrystalline cellulose, sodium starch glycolate and yellow aluminum lake (100 mg tablets only) |
APO-LAMOTRIGINE 25 mg Tablets: Each white, shield-shaped, flat faced, radial- edge tablet, scored and engraved "25" on one side, other side "APO" contains 25 mg of lamotrigine. Available in bottles of 100 and 500 tablets.
APO-LAMOTRIGINE 100 mg Tablets: Each peach, shield-shaped, flat faced, bevelled edge tablet, scored and engraved "LAM" over "100" on one side and engraved "APO" on the other side, contains 100 mg of lamotrigine. Available in bottles of 100 and 500 tablets.
APO-LAMOTRIGINE 150 mg Tablets: Each cream, shield-shaped, flat faced, bevelled edge tablet, scored and engraved "LAM" over "150" on one side and engraved "APO" on the other side, contains 150 mg of lamotrigine. Available in bottles of 60 and 100 tablets.
7 WARNINGS AND PRECAUTIONS
Please see the 3 SERIOUS WARNINGS AND PRECAUTIONS BOX.
General
Acute Multi-organ Failure
Multi-organ failure, which in some cases has been fatal or irreversible, has been observed in patients receiving lamotrigine. Fatalities associated with multi-organ failure and various degrees of hepatic failure have been reported in 2 of 3,796 adult patients and 4 of 2,435 pediatric patients who received lamotrigine in epilepsy clinical trials. No such fatalities have been reported in bipolar patients in clinical trials. Rare fatalities from multi-organ failure have also been reported in compassionate plea and postmarketing use. The majority of these deaths occurred in association with other serious medical events, including status epilepticus and overwhelming sepsis, and hantavirus, making it difficult to identify the initial cause.
Additionally, 3 patients (a 45-year-old woman, a 3.5-year-old boy, and an 11-year-old girl) developed multi-organ dysfunction and disseminated intravascular coagulation 9 to 14 days after lamotrigine was added to their AED regimens. Rash and elevated transaminases were also present in all patients and rhabdomyolysis was noted in 2 patients. Both pediatric patients were receiving concomitant therapy with valproate, while the adult patient was being treated with carbamazepine and clonazepam. All patients subsequently recovered with supportive care after treatment with lamotrigine was discontinued.
Dihydrofolate Reductase
Lamotrigine was shown to be a weak inhibitor of dihydrofolate reductase in vitro, hence there is a possibility of interference with folate metabolism during long-term therapy (see 7.1.1 Pregnant Women). In clinical studies, lamotrigine did not affect blood folate concentrations or associated hematologic parameters.
Drug Discontinuation
Abrupt discontinuation of any antiepileptic drug (AED) in a responsive patient with epilepsy may provoke rebound seizures. In general, withdrawal of an AED should be gradual to minimize this risk. Unless safety concerns (i.e. rash) require a more rapid withdrawal, the dose of lamotrigine should be tapered over a period of at least two weeks (see 4 DOSAGE AND ADMINISTRATION).
Estrogen-containing Products Including Hormonal Contraceptives
Patients taking APO-LAMOTRIGINE should be advised not to start or stop their estrogen-containing products including oral contraceptives and hormonal replacement therapy (HRT) without consulting their physician. Close clinical monitoring and significant adjustments in the maintenance dose of lamotrigine may be required (see 9.4 Drug-Drug Interactions, Oral Contraceptives; 8.5 Post-Market Adverse Reactions, Oral Contraceptives and 4 DOSAGE AND ADMINISTRATION, Starting Lamotrigine in Women Taking Oral Contraceptives, 4.2 Recommended Dose and Dosage Adjustment, Use With Other Estrogen-containing Products).
Gradual transient increases in lamotrigine levels may occur during the week of no active hormone preparation (pill-free week), as much as 2-fold at the end of the week, for women not also taking a drug that increases the clearance of lamotrigine (see 9.4 Drug-Drug Interactions, Oral Contraceptives).
Interactions with Antiepileptic Drugs
In a multidrug regimen, antiepileptic drugs may affect lamotrigine clearance, and dosage adjustment of APO-LAMOTRIGINE might be required (see 4 DOSAGE AND ADMINISTRATION, and 9 DRUG INTERACTIONS).
Other Products Containing Lamotrigine
Lamotrigine tablets should not be administered to patients currently being treated with any other preparation containing lamotrigine without consulting a doctor.
Potential Medication Errors
Medication errors involving lamotrigine have occurred. In particular, the name lamotrigine can be confused with the names of other commonly used medications. To reduce the potential of medication errors, write and say APO-LAMOTRIGINE clearly. To avoid the medication error of using the wrong drug, patients should be strongly advised to visually inspect their tablets to verify that they are APO-LAMOTRIGINE, each time they fill their prescription.
Patients with Special Diseases and Conditions
Clinical experience with lamotrigine in patients with concomitant illness is limited. Caution is advised when using APO-LAMOTRIGINE in patients with diseases or conditions that could affect the metabolism or elimination of the drug.
Cardiovascular
Brugada-type ECG
Arrhythmogenic ST-T abnormality and typical Brugada ECG pattern has been reported in patients treated with lamotrigine. The use of lamotrigine should be carefully considered in patients with Brugada syndrome (see 10.2 Pharmacodynamics).
Cardiac Rhythm Conduction Abnormalities
One placebo-controlled trial that compared electrocardiograms at baseline and during treatment, demonstrated a mild prolongation of the P-R interval associated with lamotrigine administration. The prolongation was statistically significant but clinically insignificant. Patients with significant cardiovascular disease or electrocardiographic abnormalities were, however, systematically excluded from clinical trials. Thus, APO-LAMOTRIGINE should be used with caution in patients with cardiac conduction abnormalities, and in patients taking concomitant medications which depress AV conduction.
In vitro testing showed that lamotrigine is a weak cardiac sodium channel blocker at therapeutic concentrations, similar to known Class IB antiarrhythmic agents. Based on these in vitro findings, lamotrigine could potentially slow ventricular conduction (by causing QRS prolongation) and induce proarrhythmia. This can lead to sudden death in patients with clinically significant structural or functional heart disease such as heart failure, valvular heart disease, congenital heart disease, conduction system disease, ventricular arrhythmias, cardiac channelopathies (e.g., Brugada syndrome), clinically important ischemic heart disease, or multiple risk factors for coronary artery disease. Concomitant use of other sodium channel blockers (e.g., some other anti-epileptic medications) may further increase the risk of proarrhythmia. Therefore, any expected or observed benefit of lamotrigine for those patients must be carefully weighed against the potential risks for serious or fatal cardiac events (see 10.2 Pharmacodynamics).
Driving and Operating Machinery
Patients with uncontrolled epilepsy should not drive or handle potentially dangerous machinery. During clinical trials common adverse effects included dizziness, ataxia, drowsiness, diplopia, and blurred vision. Patients should be advised to refrain from activities requiring mental alertness or physical coordination until they are sure that APO-LAMOTRIGINE does not affect them adversely.
Hematologic
Blood Dyscrasias
There have been reports of blood dyscrasias that may or may not be associated with the hypersensitivity syndrome. These have included neutropenia, leukopenia, anemia, thrombocytopenia, pancytopenia, and, rarely, aplastic anemia and pure red cell aplasia.
Hepatic/Biliary/Pancreatic
Results from a single dose pharmacokinetic study indicate that the apparent clearance of lamotrigine decreased in subjects with Grades A, B or C hepatic impairment. A reduced dosage should be used for all hepatically impaired patients, and APO-LAMOTRIGINE should be administered with caution particularly in those patients with severe hepatic impairment (see 4.2 Recommended Dose and Dose Adjustment and 10.3 Pharmacokinetics).
Immune
- Haemophagocytic lymphohistiocytosis (HLH) has occurred in pediatric and adult patients taking lamotrigine for various indications (see 8.5 Post-Market Adverse Reactions). It is a life-threatening syndrome of pathologic immune activation characterized by clinical signs and symptoms of extreme systemic inflammation and is associated with high mortality rates if not recognized early and treated. Common findings include fever, hepatosplenomegaly, rash, lymphadenopathy, neurologic symptoms, cytopenias, high serum ferritin, hypertriglyceridaemia, abnormal liver and renal function tests, and coagulation abnormalities. In cases of HLH reported with lamotrigine, patients have presented with signs of systemic inflammation (e.g., fever, rash, hepatosplenomegaly, and organ system dysfunction) and blood dyscrasias (e.g., neutropenia, thrombocytopenia, anemia, etc.). Symptoms have been reported to occur within approximately 1 to 4 weeks following lamotrigine initiation. Patients who develop these signs and symptoms should be immediately evaluated and a diagnosis of HLH should be considered. If an alternative etiology for the signs or symptoms of HLH cannot be established, APO-LAMOTRIGINE should be discontinued and other treatment options considered (See 7 WARNINGS AND PRECAUTIONS, Drug Discontinuation). The recommended initial dose and subsequent dose escalations of APO-LAMOTRIGINE should not be exceeded.
- Serious skin rashes (see 3 SERIOUS WARNINGS AND PRECAUTIONS BOX and 7 WARNINGS AND PRECAUTIONS, Skin).
Hypersensitivity
The 100 mg tablet coating contains an azo dye (FD&C Yellow No. 6 aluminium lake) which may cause allergic reactions.
Monitoring and Laboratory Tests
The relationship between clinical efficacy and plasma concentrations has not been clearly established. Based on the possible pharmacokinetic interactions between lamotrigine and other drugs including AEDs, monitoring of the plasma levels of lamotrigine and concomitant drugs may be indicated, particularly during dosage adjustments. In general, clinical judgment should be exercised regarding monitoring of plasma levels of lamotrigine and other drugs and whether or not dosage adjustments are necessary.
Neurologic
Aseptic Meningitis
Therapy with lamotrigine increases the risk of developing aseptic meningitis. Because of the potential for serious outcomes of untreated meningitis due to other causes, patients should also be evaluated for other causes of meningitis and treated as appropriate.
Postmarketing cases of aseptic meningitis have been reported in pediatric and adult patients taking lamotrigine for various indications. Symptoms upon presentation have included headache, fever, nausea, vomiting, and nuchal rigidity. Rash photophobia, myalgia, chills, altered consciousness, and somnolence were also noted in some cases. Symptoms have been reported to occur within 1 to 40 days following the initiation of treatment. In most cases, symptoms were reported to resolve after discontinuation of lamotrigine. Re-exposure resulted in a rapid return of symptoms (from within 30 minutes to 1 day following re-initiation of treatment) that were frequently more severe. Some of the patients treated with lamotrigine who developed aseptic meningitis had underlying diagnoses of systemic lupus erythematosus or other autoimmune diseases. Lamotrigine should not be restarted in patients who have discontinued due to aseptic meningitis associated with prior treatment of lamotrigine.
Cerebrospinal fluid (CSF) analysed at the time of clinical presentation in reported cases was characterized by a mild to moderate pleocytosis, normal glucose levels, and mild to moderate increase in protein. CSF white blood cell count differentials showed a predominance of neutrophils in a majority of the cases, although a predominance of lymphocytes was reported in approximately one third of the cases. Some patients also had new onset of signs and symptoms of involvement of other organs (predominantly hepatic and renal involvement) which may suggest that in these cases the aseptic meningitis observed was part of a hypersensitivity reaction.
Status Epilepticus
There are reports in the literature that severe convulsive seizures including status epilepticus may lead to rhabdomyolysis, multi-organ dysfunction and disseminated intravascular coagulation, sometimes with fatal outcome. Similar cases have occurred in association with the use of lamotrigine.
Psychiatric
Suicidal Behaviour and Ideation
Symptoms of depression and /or bipolar disorder may occur in patients with epilepsy, and there is evidence that patients with epilepsy and bipolar disorder have an elevated risk for suicidality.
25 to 50% of patients with bipolar disorder attempt suicide at least once and may experience worsening of their depressive symptoms and/or the emergence of suicidal ideation and behaviours (suicidality) whether or not they are taking medications for bipolar disorder, including lamotrigine.
Suicidal ideation and behaviour have been reported in patients treated with antiepileptic agents in several indications.
All patients treated with antiepileptic drugs, irrespective of indication, should be monitored for signs of suicidal ideation and behaviour and appropriate treatment should be considered. Patients (and caregivers of patients) should be advised to seek medical advice should signs of suicidal ideation or behaviour emerge.
An FDA meta-analysis of randomized placebo controlled trials, in which antiepileptic drugs were used for various indications, has shown a small increased risk of suicidal ideation and behaviour in patients treated with these drugs. The mechanism of this risk is not known, and the available data do not exclude the possibility of an increased risk for lamotrigine.
There were 43,892 patients treated in the placebo controlled clinical trials that were included in the meta-analysis. Approximately 75% of patients in these clinical trials were treated for indications other than epilepsy and, for the majority of non-epilepsy indications the treatment (antiepileptic drug or placebo) was administered as monotherapy. Patients with epilepsy represented approximately 25% of the total number of patients treated in the placebo controlled clinical trials and, for the majority of epilepsy patients, treatment (antiepileptic drug or placebo) was administered as adjunct to other antiepileptic agents (i.e., patients in both treatment arms were being treated with one or more antiepileptic drug). Therefore, the small increased risk of suicidal ideation and behaviour reported from the meta-analysis (0.43% for patients on antiepileptic drugs compared to 0.24% for patients on placebo) is based largely on patients that received monotherapy treatment (antiepileptic drug or placebo) for non-epilepsy indications. The study design does not allow an estimation of the risk of suicidal ideation and behaviour for patients with epilepsy that are taking antiepileptic drugs, due both to this population being the minority in the study, and the drug-placebo comparison in this population being confounded by the presence of adjunct antiepileptic drug treatment in both arms.
Renal
A study in individuals with chronic renal failure (not receiving other AEDs) indicated that the elimination half-life of unchanged lamotrigine is prolonged relative to individuals with normal renal function (see 10 CLINICAL PHARMACOLOGY). APO-LAMOTRIGINE should be used with caution in patients with severe renal impairment.
Skin
- Serious and sometimes fatal skin rashes, including Stevens-Johnson Syndrome (SJS) and Toxic Epidermal Necrolysis (TEN), have occurred with the use of lamotrigine (see 3 SERIOUS WARNINGS AND PRECAUTIONS BOX).
Drug Reaction with Eosinophilia and Systemic Symptoms
Multi-organ hypersensitivity reactions, also known as Drug Reaction with Eosinophilia and Systemic Symptoms (DRESS), have occurred with lamotrigine. Some have been fatal or life threatening. DRESS typically, although not exclusively, presents with fever, rash, facial oedema, and/or lymphadenopathy in association with other organ system involvement, such as hepatitis, nephritis, hematologic abnormalities, aseptic meningitis, myocarditis, or myositis, sometimes resembling an acute viral infection (see 8 ADVERSE REACTIONS). Eosinophilia is often present. This disorder is variable in its expression and other organ systems not noted here may be involved. The syndrome shows a wide spectrum of clinical severity and may rarely lead to disseminated intravascular coagulation (DIC) and multi-organ failure.
It is important to note that early manifestations of hypersensitivity (e.g., fever, lymphadenopathy) may be present even though a rash is not evident. If such signs or symptoms are present, the patient should be evaluated immediately. APO-LAMOTRIGINE should be discontinued if an alternative etiology for the signs or symptoms cannot be established.
Prior to initiation of treatment with APO-LAMOTRIGINE, the patient should be instructed that a rash or other signs or symptoms of hypersensitivity (e.g., fever, lymphadenopathy) may herald a serious medical event and that the patient should report any such occurrence to a physician immediately.
Asian Ancestry and Allelic variation in HLA-B
Some meta-analyses have shown that human leukocyte antigen (HLA)-B*1502 allele in individuals of Asian (primarily Han Chinese and Thai†) origin is associated with the risk of developing SJS/TEN when treated with lamotrigine. If patients are known to be carrying this genetic variant, the benefits of treatment with lamotrigine should be carefully weighed against the risk of developing SJS/TEN. Should signs and symptoms suggest a severe skin reaction such as SJS or TEN, lamotrigine should be withdrawn at once, under clinical supervision.
Many HLA-B*1502-positive Asian patients treated with lamotrigine will not develop SJS/TEN, and these reactions can still occur infrequently in HLA-B*1502-negative patients of any ethnicity. The role of other possible factors in the development of, and morbidity from, SJS/TEN, such as antiepileptic drug (AED) dose, compliance, concomitant medications, co-morbidities, and the level of dermatologic monitoring have not been studied.
In addition, it should be kept in mind that the majority of lamotrigine -treated patients who will experience SJS/TEN have this reaction within the first few months of treatment.
† The following rates provide a rough estimate of the prevalence of HLA-B*1502 in various populations. Greater than 15% of the population is reported positive in Hong Kong, Thailand, Malaysia, and parts of the Philippines, compared to about 10% in Taiwan and 4% in North China. South Asians, including Indians, appear to have intermediate prevalence of HLA-B*1502, averaging 2 to 4%, but this may be higher in some groups. HLA-B*1502 is present in < 1% of the population in Japan and Korea. HLA-B*1502 is largely absent in individuals not of Asian origin (e.g., Caucasians, African-Americans, Hispanics, and Native Americans). The estimated prevalence rates have limitations due to the wide variability in rates that exist within ethnic groups, the difficulties in ascertaining ethnic ancestry and the likelihood of mixed ancestry.
Photosensitivity
There have also been reports of photosensitivity reactions associated with lamotrigine use. If lamotrigine-associated photosensitivity is suspected in a patient showing signs of photosensitivity (such as an exaggerated sunburn), treatment discontinuation should be considered. If continued treatment with lamotrigine is considered clinically justified, the patient should be advised to avoid exposure to sunlight and artificial UV light and take protective measures (e.g. use of protective clothing and sunscreens).
Skin-related events
Serious rashes requiring hospitalisation, including rare reports of fatalities, have occurred with lamotrigine (see 3 SERIOUS WARNINGS AND PRECAUTIONS BOX).
The risk of serious skin rashes is higher in children than in adults.
In adult controlled studies of adjunctive lamotrigine therapy, the incidence of rash (usually maculopapular and/or erythematous) in patients receiving lamotrigine was 10% compared with 5% in placebo patients. The rash usually occurred within the first eight weeks of therapy and resolved during continued administration of lamotrigine. Lamotrigine was discontinued because of rash in 1.1% of adult patients in controlled studies and 3.8% of all patients in all studies. The rate of rash-related withdrawal in clinical studies was higher with more rapid initial titration dosing, and in patients receiving concomitant valproic acid (VPA), particularly in the absence of AEDs that induce lamotrigine glucuronidation. See Table 7 and Table 8; see also 4 DOSAGE AND ADMINISTRATION.
Table 7 Effect of Concomitant AEDs on Rash Associated with Lamotrigine in All Adult Controlled and Uncontrolled Clinical Trials Regardless of Dosing Escalation Scheme
| AED Group | Total Patient Number | All Rashes | Withdrawal Due to Rash | Hospitalization in Association with Rash |
| AEDs that induce lamotrigine glucuronidation1 | 1788 | 9.2% | 1.8% | 0.1% |
| AEDs that induce lamotrigine glucuronidation1 + VPA | 318 | 8.8% | 3.5% | 0.9% |
| VPA ± AEDs that neither inhibit nor induce lamotrigine glucuronidation2 | 159 | 20.8% | 11.9% | 2.5% |
| AEDs that neither inhibit nor induce lamotrigine glucuronidation2 | 27 | 18.5% | 0.0% | 0.0% |
VPA = Valproic Acid 1 AEDs that induce lamotrigine glucuronidation include carbamazepine, phenobarbital, phenytoin, and primidone 2 AEDs that neither inhibit nor induce lamotrigine glucuronidation include clonazepam, clobazam, ethosuximide, methsuximide, vigabatrin, and gabapentin | ||||
Table 8 Effect of the Initial Daily Dose1 of Lamotrigine in the Presence of Concomitant AEDs, on the Incidence of Rash Leading to Withdrawal of Treatment in Adult Add-On Clinical Trials
| AED Group | AEDs that induce lamotrigine glucuronidation2 | AEDs that induce lamotrigine glucuronidation2 + VPA | VPA±AEDs that neither inhibit nor induce lamotrigine glucuronidation3 | |||
| AED Group | AEDs that induce lamotrigine glucuronidation2 | AEDs that induce lamotrigine glucuronidation2 + VPA | VPA±AEDs that neither inhibit nor induce lamotrigine glucuronidation3 | |||
| Lamotrigine Average Daily Dose (mg) | Total Patient Number | Percentage of Patients Withdrawn | Total Patient Number | Percentage of Patients Withdrawn | Total Patient Number | Percentage of Patients Withdrawn |
| 12.5 | 9 | 0.0 | 10 | 0.0 | 51 | 7.8 |
| 25 | 3 | 0.0 | 7 | 0.0 | 58 | 12.1 |
| 50 | 182 | 1.1 | 111 | 0.9 | 35 | 5.7 |
| 100 | 993 | 1.4 | 179 | 4.5 | 15 | 40.0 |
| ≥125 | 601 | 2.8 | 11 | 18.2 | 0 | 0.0 |
VPA = valproic acid
| ||||||
Increased incidence of rash-related withdrawal was seen when initial doses were higher and titration more rapid than recommended under 4 DOSAGE AND ADMINISTRATION.
Patients with a history of allergy or rash to other antiepileptic drugs
Caution is also required when treating patients with a history of allergy or rash to other antiepileptic drugs, as it was found in two studies (n = 767 and n = 988) on the frequency of rash after treatment with lamotrigine that the rate of rash was approximately three to four times higher in patients with such a history than those without.
Restarting APO-LAMOTRIGINE Therapy
It is recommended that APO-LAMOTRIGINE not be restarted in patients who discontinued due to rash associated with prior treatment with APO-LAMOTRIGINE unless the potential benefits clearly outweigh the risks. If the decision is made to restart a patient who has discontinued APO-LAMOTRIGINE for any reason, the need to restart with the initial dosing recommendations should be assessed. The greater the interval of time since the previous dose, the greater consideration should be given to restarting with the initial dosing recommendations. If a patient has discontinued APO-LAMOTRIGINE for a period of more than 5 half-lives, it is recommended that initial dosing recommendations and guidelines be followed. The half-life of lamotrigine is affected by other concomitant medications (see 10.3 Pharmacokinetics and 4.1 Dosing Considerations).
7.1 Special Populations
7.1.1 Pregnant Women
APO-LAMOTRIGINE should only be used during pregnancy if the expected benefits outweigh the potential risks. If therapy with APO-LAMOTRIGINE is considered necessary during pregnancy, the lowest possible therapeutic dose is recommended.
Physiological changes during pregnancy may affect lamotrigine levels and/or therapeutic effect. There have been reports of decreased lamotrigine levels during pregnancy. Appropriate clinical management of pregnant women during lamotrigine therapy should be ensured.
Studies in mice, rats and rabbits given lamotrigine orally or intravenously revealed no evidence of teratogenicity, however, maternal and secondary fetal toxicity producing reduced fetal weight and/or delayed ossification in mice and rats were observed.
In rats, enhanced fetal as well as post-natal mortality was observed when lamotrigine was administered during late gestation and through the early post-natal period. These effects were observed at the expected clinical exposure. Lamotrigine reduced fetal folic acid levels in rats. Folic acid deficiency is assumed to be associated with an enhanced risk of congenital malformations in animals as well as in humans. Intake of folic acid when planning pregnancy and during early pregnancy may be considered.
Studies in rats and rabbits indicate that lamotrigine crosses the placenta; placental and fetal plasma concentrations of lamotrigine are comparable to levels in maternal plasma. In studies where simultaneous maternal and umbilical cord samples were taken, the ratio of umbilical cord/maternal lamotrigine plasma concentrations were generally close to unity (range of 0.4 to 1.4).
Pregnancy Registries
Postmarketing data from six prospective pregnancy registries have documented outcomes in approximately 8700 women exposed to lamotrigine monotherapy during the first trimester of pregnancy. Two registries have reported an increase in the risk of isolated oral cleft (isolated) malformations with exposure to lamotrigine in the first trimester, over both the study reference population and reported background rates from the literature. The observed risk of malformations following first trimester monotherapy exposure ranged from 2.0% in the North American Registry to 4.9% in the Swedish Registry as compared to unexposed groups.
North American Registry
The North American Anti-Epileptic Drug Registry reported rates of 7.3/1000 for lamotrigine exposures in the registry with n = 684 vs. 0.70/1000 for the reference population and 0.50 to 2.16/1000 for the background rates.
Swedish Registry
The Swedish Medical Birth Register reported rates of 9.9/1000 for lamotrigine exposures in the registry with n=403 vs 2.0/1000 for the registry reference population and 0.50 to 2.16/1000 for the background rates. In the remaining registries with approximately 3000 women, 4 cases of isolated oral cleft malformation were found (1.3/1000 vs. 0.50 to 2.16/1000 for the background rates).
EUROCAT
The European Network of Congenital Anomaly and Twin Registries (EUROCAT) is a network of 40 registries across 20 European countries. The results of a case control design using the EUROCAT dataset demonstrated that the risk of development of oral clefts in the newborn infants was similar to other malformations (e.g., club foot, limb, heart and respiratory defects) following exposure to lamotrigine in the first trimester. Within the EUROCAT network, rates of exposure to lamotrigine in the first trimester of pregnancy were similar among 4571 non chromosomal, isolated oral cleft cases and 80,052 non chromosomal, non oral cleft defect controls.
The data on use of lamotrigine in polytherapy combinations are insufficient to assess whether the risk of malformation associated with other agents is affected by concomitant lamotrigine use.
To provide information regarding the effects of in utero exposure to APO-LAMOTRIGINE, physicians are advised to recommend that pregnant patients taking APO-LAMOTRIGINE enroll in the North American Antiepileptic Drug (NAAED) Pregnancy Registry. This can be done by calling the toll-free number 1-888-233-2334 and must be done by patients themselves. Information on the registry can also be found at the website http://www.aedpregnancyregistry.org/.
Labour and Delivery
The effect of lamotrigine on labour and delivery in humans is unknown.
7.1.2 Breast-feeding
Lamotrigine has been reported to pass into breast milk resulting in total lamotrigine levels in infant’s plasma, including neonates as well as older infants, of up to approximately 50% of the mother’s plasma. Therefore, in some breast-fed infants, plasma concentrations of lamotrigine may reach levels at which pharmacological effects do occur.
Because of the potential for adverse reactions from lamotrigine in nursing infants, breast-feeding while taking this medication is not recommended. Should a woman breast-feed while on therapy with lamotrigine, the infant should be monitored for adverse effects, such as sedation, rash and poor weight gain. Events including apnea, drowsiness, and poor sucking have been reported in infants who have been human milk-fed by mothers using lamotrigine; whether or not these events were caused by lamotrigine is unknown.
7.1.4 Geriatrics
As the pharmacokinetics in this age group do not differ significantly from a non-elderly adult population, no dosage adjustment from the recommended adult schedule is required (see 4.2 Recommended Dose and Dose Adjustment, 8.2 Clinical Trial Adverse Reactions and 10.3 Pharmacokinetics).
8 ADVERSE REACTIONS
8.1 Adverse Reaction Overview
Serious skin rashes, including Erythema multiforme, Stevens Johnson Syndrome, and Toxic Epidermal Necrolysis (Lyell Syndrome) have been reported. Although the majority recover following drug withdrawal, some patients experience irreversible scarring and there have been rare cases of associated death (see 7 WARNINGS AND PRECAUTIONS).
Adverse experiences in patients receiving lamotrigine were generally mild, occurred within the first two weeks of therapy, and resolved without discontinuation of the drug.
8.2 Clinical Trial Adverse Reactions
Clinical trials are conducted under very specific conditions. The adverse reaction rates observed in the clinical trials; therefore, may not reflect the rates observed in practice and should not be compared to the rates in the clinical trials of another drug. Adverse reaction information from clinical trials may be useful in identifying and approximating rates of adverse drug reactions in real-world use.
Commonly Observed
The most commonly observed adverse experiences associated with the use of adjunctive therapy with lamotrigine (incidence of at least 10%) were dizziness, headache, diplopia, somnolence, ataxia, nausea, and asthenia.
Dizziness, diplopia, ataxia and blurred vision were dose-related and occurred more commonly in patients receiving carbamazepine in combination with lamotrigine than in patients receiving other AEDs that induce lamotrigine glucuronidation in combination with lamotrigine. Reduction of the daily dose and/or alteration of the timing of doses of concomitant antiepileptic drugs and/or lamotrigine may reduce or eliminate these symptoms. Clinical data suggest a higher incidence of rash in patients who are receiving concomitant valproic acid, or non-inducing AEDs (see 7 WARNINGS AND PRECAUTIONS, Skin-related events, Table 7).
Adverse Events Associated with Discontinuation of Treatment
Across all adult add-on studies, the most common adverse experiences associated with discontinuation of lamotrigine were rash, dizziness, headache, ataxia, nausea, diplopia, somnolence, seizure exacerbation, asthenia, and blurred vision. In controlled clinical trials, 6.9% of the 711 patients receiving lamotrigine discontinued therapy due to an adverse experience, versus 2.9% of the 419 patients receiving placebo. Of 3501 patients and volunteers who received lamotrigine in premarketing clinical studies, 358 (10.2%) discontinued therapy due to an adverse experience.
Serious Adverse Events Associated with Discontinuation of Treatment
Discontinuation due to an adverse experience classified as serious occurred in 2.3% of adult patients and volunteers who received lamotrigine in the pre-market studies. Rash accounted for almost half of the discontinuations due to serious adverse experiences. More rapid initial titration of lamotrigine, and concomitant use of valproic acid were associated with higher incidences of rash-related withdrawal in clinical studies (see 7 WARNINGS AND PRECAUTIONS, Skin-related events, Table 8).
Adult Controlled Add-on Clinical Studies
Table 9 enumerates adverse experiences that occurred with an incidence of 2% or greater among refractory patients with epilepsy treated with lamotrigine.
Table 9 Percentage of Treatment - Emergent Adverse Experiences in Adult Placebo or Comparator-Controlled Clinical Studies1
| Body System / Adverse Experience4 | ADULTS (ADJUNCTIVE THERAPY)2 | ELDERLY (MONOTHERAPY)3 | |
| Body System / Adverse Experience4 | ADULTS (ADJUNCTIVE THERAPY)2 | ELDERLY (MONOTHERAPY)3 | |
| Body System / Adverse Experience4 | ADULTS (ADJUNCTIVE THERAPY)2 | ELDERLY (MONOTHERAPY)3 | |
Lamotrigine (and other AEDs) | Placebo (and other AEDs) | Lamotrigine | |
Lamotrigine (and other AEDs) | Placebo (and other AEDs) | Lamotrigine | |
Lamotrigine (and other AEDs) | Placebo (and other AEDs) | Lamotrigine | |
| Total number of Patients | (n = 711) | (n = 419) | (n = 102) |
| Total number of Patients | (n = 711) | (n = 419) | (n = 102) |
| Total number of Patients | (n = 711) | (n = 419) | (n = 102) |
| BODY AS A WHOLE | |||
| Headache | 29.1 | 19.1 | 8.8 |
| Accidental Injury | 9.1 | 8.6 | 8.8 |
| Asthenia | 8.6 | 8.8 | 4.9 |
| Flu Syndrome | 7.0 | 5.5 | 4.9 |
| Pain | 6.2 | 2.9 | 5.9 |
| Back Pain | 5.8 | 6.2 | 3.9 |
| Fever | 5.5 | 3.6 | 0.9 |
| Abdominal Pain | 5.2 | 3.6 | 3.9 |
| Infection | 4.4 | 4.1 | 5.9 |
| Neck Pain | 2.4 | 1.2 | 0 |
| Malaise | 2.3 | 1.9 | 4.9 |
| Seizure Exacerbation | 2.3 | 0.5 | n/a |
| CARDIOVASCULAR | |||
| Chest pain | n/a | n/a | 2.9 |
| Syncope | n/a | n/a | 2.9 |
| Cerebrovascular accident | n/a | n/a | 3.9 |
| DIGESTIVE | |||
| Nausea | 18.6 | 9.5 | 8.8 |
| Vomiting | 9.4 | 4.3 | 8.8 |
| Diarrhea | 6.3 | 4.1 | 6.9 |
| Dyspepsia | 5.3 | 2.1 | 5.9 |
| Constipation | 4.1 | 3.1 | 8.9 |
| Tooth Disorder | 3.2 | 1.7 | 0 |
| MUSCULOSKELETAL | |||
| Myalgia | 2.8 | 3.1 | 0.9 |
| Arthralgia | 2.0 | 0.2 | 2.9 |
| NERVOUS | |||
| Dizziness | 38.4 | 13.4 | 9.8 |
| Ataxia | 21.7 | 5.5 | 0 |
| Somnolence | 14.2 | 6.9 | 11.8 |
| Incoordination | 6.0 | 2.1 | 12.7 |
| Insomnia | 5.6 | 1.9 | 3.9 |
| Tremor | 4.4 | 1.4 | 0.9 |
| Depression | 4.2 | 2.6 | 4.9 |
| Anxiety | 3.8 | 2.6 | 0.9 |
| Convulsion | 3.2 | 1.2 | 1.9 |
| Irritability | 3.0 | 1.9 | 0 |
| Speech Disorder | 2.5 | 0.2 | 0.9 |
| Memory Decreased | 2.4 | 1.9 | n/a |
Memory Decreased (Memory Rating Question) | n/a | n/a | 19.6 |
| RESPIRATORY | |||
| Rhinitis | 13.6 | 9.3 | 0.9 |
| Pharyngitis | 9.8 | 8.8 | 1.9 |
| Cough Increased | 7.5 | 5.7 | 2.9 |
| Respiratory Disorder | 5.3 | 5.5 | 0.9 |
| Asthma | n/a | n/a | 3.0 |
| SKIN AND APPENDAGES | |||
| Rash | 10.0 | 5.0 | 8.8 |
| Pruritus | 3.1 | 1.7 | 5.9 |
| Herpes Zoster | n/a | n/a | 3.0 |
| Eczema | n/a | n/a | 2.0 |
| Ulcer Skin | n/a | n/a | 2.0 |
| SPECIAL SENSES | |||
| Diplopia | 27.6 | 6.7 | 0 |
| Blurred Vision | 15.5 | 4.5 | 0 |
| Vision Abnormality | 3.4 | 1.0 | 0 |
| UROGENITAL | |||
| Female Patients | (n = 365) | (n = 207) | (n = 47) |
| Dysmenorrhea | 6.6 | 6.3 | n/a |
| Menstrual Disorder | 5.2 | 5.8 | n/a |
| Vaginitis | 4.1 | 0.5 | 0 |
- 1. Patients from the studies summarized in the first two columns were receiving 1 to 3 concomitant enzyme-inducing antiepileptic drugs in addition to lamotrigine or placebo. Patients from the single study summarized in the last column were compared to n = 48 patients receiving carbamazepine. Patients may have reported multiple adverse experiences during the study or at discontinuation. Thus, patients may be included in more than one category.
- 2. Studies 05, 06, 16 (US) & 16, 21, 35 & 37 (UK)
- 3. Study 105 - 124 - C93
- 4.
All Adverse Experiences reported by at least 2% of patients treated with either lamotrigine add-on or monotherapy are included.
n/a: Not applicable
Other Events Observed During Clinical Studies
During clinical testing, multiple doses of lamotrigine were administered to 3501 patients and volunteers. The conditions and duration of exposure to lamotrigine during these clinical studies varied greatly. Studies included monotherapy and pediatric trials. A substantial proportion of the exposure was gained in open, uncontrolled clinical studies. Adverse experiences associated with exposure to lamotrigine were recorded by clinical investigators using terminology of their own choosing. Consequently, it is not possible to provide a meaningful estimate of the proportion of individuals experiencing adverse events without first grouping similar types of adverse experiences into a smaller number of standardized event categories.
Since the adverse experiences reported occurred during treatment with lamotrigine in combination with other antiepileptic drugs, they were not necessarily caused by lamotrigine.
The following adverse events have been reported on one or more occasions by at least 1% of patients and volunteers exposed to lamotrigine: anorexia, weight gain, amnesia, concentration disturbance, confusion, emotional lability, nervousness, nystagmus, paresthesia, thinking abnormality and vertigo (all types of events are included except those already listed in Table 9).
Adult Monotherapy Clinical Studies
Withdrawals due to adverse events were reported in 42 (9.5%) of newly diagnosed patients treated with lamotrigine monotherapy. The most common adverse experiences associated with discontinuation of lamotrigine were rash (6.1%), asthenia (1.1%), headache (1.1%), nausea (0.7%) and vomiting (0.7%).
Geriatric Monotherapy Clinical Studies
A study with elderly newly-diagnosed epilepsy patients yielded rates of adverse events which were generally similar to those reported in adults (see Table 9). The rate of withdrawal due to adverse events was 21.6%, with rash (3%), nausea (3%) and coordination abnormalities (3%) representing the most common events associated with withdrawal, followed by somnolence (2%), depression (2%), accidental injury (2%) and malaise (2%) (see 4.2 Recommended Dose and Dosage Adjustment and 10.3 Pharmacokinetics).
Adjunctive Therapy in Lennox-Gastaut Syndrome
In 169 adult and pediatric patients with Lennox Gastaut syndrome, 3.8% of patients on lamotrigine and 7.8% of patients on placebo discontinued due to adverse experiences. The most commonly reported adverse experiences that led to discontinuation were rash for patients treated with lamotrigine and deterioration of seizure control for patients treated with placebo. Fever and infection occurred at least 10% more frequently in patients ≤ 12 years of age than in patients > 12 years of age on lamotrigine. Rash occurred at least 10% more frequently in female patients than male patients on lamotrigine. Table 10 lists adverse events that occurred in at least 1% of 79 adult and pediatric patients who received lamotrigine up to 15 mg/kg per day or a maximum of 400 mg per day.
Table 10 Treatment-Emergent Adverse Experience Incidence in Placebo-Controlled Add-On Trial in Adult and Pediatric Patients with Lennox Gastaut Syndrome1
| Body System / Adverse Experience | Percent of Patients Receiving Lamotrigine (n = 79) | Percent of Patients Receiving Placebo (n = 90) |
| Body System / Adverse Experience | Percent of Patients Receiving Lamotrigine (n = 79) | Percent of Patients Receiving Placebo (n = 90) |
| Body as a whole | ||
| Infection | 13 | 8 |
| Accidental injury | 9 | 7 |
| Flu Syndrome | 5 | 0 |
| Asthenia | 3 | 1 |
| Abdominal Pain | 3 | 0 |
| Back Pain | 1 | 0 |
| Edema of the face | 1 | 0 |
| Lab test abnormal | 1 | 0 |
| Pain | 1 | 0 |
| Cardiovascular | ||
| Hemorrhage | 3 | 0 |
| Digestive | ||
| Vomiting | 9 | 7 |
| Constipation | 5 | 2 |
| Diarrhea | 4 | 2 |
| Nausea | 4 | 1 |
| Anorexia | 3 | 1 |
| Stomatitis aphtha | 1 | 0 |
| Tooth disorder | 1 | 0 |
| Endocrine | ||
| Cushing's syndrome | 1 | 0 |
| Hypothyroidism | 1 | 0 |
| Hemic and lymphatic | ||
| Lymphadenopathy (enlarged cervical nodes) | 1 | 0 |
| Nervous system | ||
| Ataxia | 4 | 1 |
| Convulsions | 4 | 1 |
| Tremor | 3 | 0 |
| Agitation | 1 | 0 |
| Coordination | 1 | 0 |
| Dizziness | 1 | 0 |
| Emotional lability | 1 | 0 |
| Nervousness | 1 | 0 |
| Vertigo | 1 | 0 |
| Respiratory | ||
| Pharyngitis | 14 | 10 |
| Bronchitis | 9 | 7 |
| Pneumonia | 3 | 0 |
| Dyspnea | 1 | 0 |
| Skin | ||
| Rash | 9 | 7 |
| Eczema | 4 | 0 |
| Nail disorder | 1 | 0 |
| Special senses | ||
| Blepharitis | 1 | 0 |
| Conjunctivitis | 1 | 0 |
| Keratitis | 1 | 0 |
| Ear pain | 1 | 0 |
| Eye pain | 1 | 0 |
| Urogenital | ||
| Urinary tract infection | 3 | 0 |
| Balanitis | 2 | 0 |
| Penis disorder | 2 | 0 |
1 = the most frequently reported adverse reactions in children ≤ 12 years of age in both treatment groups were pharyngitis, fever and infection.
8.3 Less Common Clinical Trial Adverse Reactions
Less common clinical trial adverse reactions that occurred with a frequency ≥1% and <2% are listed below.
Body as a Whole: chest pain, chills
Cardiovascular: cerebral infarction, hot flashes, palpitations
Gastrointestinal: dry mouth
Musculoskeletal: joint disorder, myasthenia
Nervous System: dream abnormality, dysarthria, grand mal convulsion, hostility, hypertension, hypesthesia, mind racing, muscle spasm, sleep disorder
Metabolic: hyperkalemia, peripheral edema
Skin: acne, alopecia
Special Senses: eye disorder
Urogenital: amenorrhea, dysuria
8.5 Post-Market Adverse Reactions
In addition to the adverse experiences reported during clinical testing of lamotrigine, the following adverse experiences have been reported in patients receiving marketed lamotrigine and from worldwide investigational use. These adverse experiences have not been listed above, and data are insufficient to establish causation.
Body as a Whole: hypersensitivity reaction/hypersensitivity syndrome*, multi-organ failure, progressive immunosuppression, tiredness
* Rash has also been reported as part of Drug Reaction with Eosinophilia and Systemic Symptoms (DRESS); also known as hypersensitivity syndrome. This condition is associated with a variable pattern of systemic symptoms (see 7 WARNINGS AND PRECAUTIONS, Skin).
Gastrointestinal: Esophagitis
Cardiac disorders: stress cardiomyopathy, atrioventricular block, ventricular fibrillation, ventricular tachycardia, QRS prolongation, ventricular extrasystoles, PR-prolongation
Hematologic and Lymphatic: Hematological abnormalities (anemia, agranulocytosis, aplastic anemia, disseminated intravascular coagulation, hemolytic anemia, leucopenia, neutropenia, pancytopenia, red cell aplasia thrombocytopenia), lymphadenopathy*, haemophagocytic lymphohistiocytosis (HLH) (see 7 WARNINGS AND PRECAUTIONS, Immune), pseudolymphoma**
*There have been reported cases of lymphadenopathy in the absence of hypersensitivity reactions, in patients with or without previous history, and taking lamotrigine alone or in combination with other medications (including other AEDs). Discontinuation of lamotrigine or, in some cases, dose reduction resolved the reaction.
**There have been reports of pseudolymphoma, including cutaneous pseudolymphoma, with gradual development or delayed onset within months of starting treatment with lamotrigine; in most reported cases, discontinuation of lamotrigine resolved the reaction.
Hepatobiliary Tract and Pancreas: elevations of liver function tests, hepatic dysfunction, including hepatic failure*, pancreatitis
*Hepatic dysfunction usually occurs in association with hypersensitivity reactions, but isolated cases have been reported without overt signs of hypersensitivity.
Immunologic: hypogammaglobulinaemia*, lupus-like reaction, vasculitis
*There have been rare reports of reduced serum immunoglobulin levels in patients receiving lamotrigine. In some cases, discontinuation of lamotrigine with or without administration of intravenous immunoglobulin resolved the reaction. Serum immunoglobulin levels should be measured in lamotrigine-treated patients who experience recurrent infections.
Lower Respiratory: apnea
Metabolism and nutrition disorders: Hyponatremia
Musculoskeletal: rhabdomyolysis (observed in patients experiencing hypersensitivity reactions)
Neurologic: aggression, aseptic meningitis*, exacerbation of parkinsonian symptoms**, extrapyramidal effects, choreoathetosis, hallucinations, movement disorders (such as tics and unsteadiness), nightmares
*There have been rare reports of aseptic meningitis in patients taking lamotrigine alone or in combination with other AEDs. In some cases, discontinuation of lamotrigine resolved this reaction (see 7 WARNINGS AND PRECAUTIONS, Hypersensitivity Reactions).
**There have been reports that lamotrigine may worsen parkinsonian symptoms in patients with pre-existing Parkinson’s disease, and isolated reports of extrapyramidal effects and choreoathetosis in patients without this underlying condition.
Oral Contraceptives: There have been post marketing reports of breakthrough seizures in patients taking lamotrigine and hormonal contraceptives. In some cases, reduced serum lamotrigine levels during co-administration with a hormonal contraceptive have been documented. Most cases have responded to lamotrigine dose increase (see 4 DOSAGE AND ADMINISTRATION, Starting Lamotrigine in Women Taking Oral Contraceptives and 9 DRUG INTERACTIONS, Oral Contraceptives).
Renal and Urinary disorders: Tubulointerstitial nephritis* (may occur in association with uveitis)
*Tubulointerstitial nephritis usually occurs in association with hypersensitivity reactions, but isolated cases have been reported without overt signs of hypersensitivity. In the absence of hypersensitivity, discontinuation of lamotrigine and treatment with steroids resolved the reaction in some cases.
Skin: Photosensitivity reaction
9 DRUG INTERACTIONS
9.2 Drug Interactions Overview
Uridine 5’-diphospho (UDP)-glucuronyl transferases (UGTs) have been identified as the enzymes responsible for metabolism of lamotrigine. Drugs that induce or inhibit glucuronidation may, therefore, affect the apparent clearance of lamotrigine. Strong or moderate inducers of the cytochrome P450 3A4 (CYP3A4) enzyme, which are also known to induce UGTs, may also enhance the metabolism of lamotrigine.
The effects of lamotrigine on the induction of specific families of mixed-function oxidase isozymes have not been systematically evaluated. Lamotrigine may induce its own metabolism, but the effect is modest and unlikely to have significant clinical consequences.
A number of drugs (see 9.4 Drug-Drug Interactions) have been shown to have little or no effect on the concentration of lamotrigine. Coadministration of such drugs would generally not be expected to result in any clinical impact. However, consideration should be given to patients whose epilepsy is especially sensitive to fluctuations in concentrations of lamotrigine.
9.3 Drug-Behavioural Interactions
Dependence Liability
No evidence of abuse potential has been associated with lamotrigine, nor is there evidence of psychological or physical dependence in humans.
9.4 Drug-Drug Interactions
The drugs listed in this table are based on either drug interaction case reports or studies, or potential interactions due to the expected magnitude and seriousness of the interaction (i.e., those identified as contraindicated).
Antiepileptic Drugs (AEDs)
The net effects of co-administration of lamotrigine with other antiepileptic drugs are summarized in Table 11. Additional details of these drug interaction studies are provided below.
Table 11 Summary of AED Interactions with lamotrigine
| AED | AED Plasma Concentration with Adjunctive LAM1 | Lamotrigine Plasma Concentration with Adjunctive AEDs2 |
Carbamazepine (CBZ) CBZ epoxide3 | No significant effect Conflicting data | ↓40% |
| Felbamate | Not evaluated | No significant effect |
| Gabapentin | Not evaluated | No significant effect |
| Lacosamide | Not evaluated | No significant effect |
| Levetiracetam | No significant effect | No significant effect |
| Oxcarbazepine | No significant effect | No significant effect |
| 10-monohydroxy oxcarbazepine metabolite | No significant effect | Not evaluated |
| Perampanel | No significant effect4 | No significant effect |
| Phenobarbital | No significant effect | ↓ 40% |
| Phenytoin (PHT) | No significant effect | ↓ 40% |
| Pregabalin | No significant effect | No significant effect |
| Primidone | No significant effect | ↓ 40% |
| Topiramate | No significant effect4 | No significant effect |
| Valproic Acid (VPA) | Decreased5 | ↑ 200% |
| VPA + PHT and/or CBZ | Not evaluated | No significant effect |
| Zonisamide | Not evaluated | No significant effect |
LAM = Lamotrigine.
↓ Decreased (induces lamotrigine glucuronidation) ↑ Increased (inhibits lamotrigine glucuronidation) | ||
Lamotrigine does not affect the plasma concentrations of concomitantly administered AEDs that induce lamotrigine glucuronidation. Antiepileptic drugs (such as phenytoin, carbamazepine, phenobarbital, and primidone) that induce cytochrome P450 enzymes also induce UGTs and therefore, enhance the metabolism of lamotrigine by increasing the plasma clearance and reducing the elimination half-life of lamotrigine (see 10 CLINICAL PHARMACOLOGY).
Carbamazepine
There have been reports of central nervous system events including dizziness, ataxia, diplopia, blurred vision, and nausea in patients taking carbamazepine following the introduction of lamotrigine tablet. These events usually resolve when the dose of carbamazepine is reduced.
Felbamate (not available in Canada)
In a cross-over study of 21 healthy male volunteers, coadministration of felbamate (1200 mg twice daily) with lamotrigine (100 mg twice daily for 10 days) appeared to have no clinically relevant effects on the pharmacokinetics of lamotrigine. Furthermore, felbamate had no significant effect on urinary excretion of total lamotrigine, unconjugated lamotrigine or N-glucuronide metabolite.
Gabapentin
Based on a retrospective analysis of plasma levels of 34 epileptic patients who received lamotrigine both with and without gabapentin, gabapentin did not appear to change the apparent clearance of lamotrigine. No information is available about the effects of gabapentin on Cmax or AUC of lamotrigine.
Lacosamide
Plasma concentrations of lamotrigine were not affected by concomitant lacosamide (200, 400, or 600 mg/day) in three placebo-controlled clinical trials in patients with partial-onset seizures.
Levetiracetam
Potential drug interactions between levetiracetam and lamotrigine were assessed by evaluating serum concentrations of both agents during placebo-controlled clinical trials. In 48 refractory epileptic patients receiving stable doses of lamotrigine, concomitant levetiracetam (1000 to 4000 mg/day) did not influence mean steady serum concentrations of lamotrigine. Similarly, lamotrigine did not influence the pharmacokinetics of levetiracetam.
Oxcarbazepine
The AUC and Cmax of oxcarbazepine and its active 10-monohydroxy oxcarbazepine metabolite were not significantly different following the addition of oxcarbazepine (600 mg twice daily) to lamotrigine (200 mg once daily) in healthy male volunteers (n = 13) compared to healthy male volunteers receiving oxcarbazepine alone (n = 13). Limited clinical data suggest a higher incidence of headache, dizziness, nausea, and somnolence with co-administration of lamotrigine and oxcarbazepine compared to lamotrigine alone or oxcarbazepine alone.
Perampanel
In a population pharmacokinetic analysis of data from three placebo-controlled clinical trials investigating adjunctive perampanel in patients with partial-onset and primary generalised tonic- clonic seizures, the highest perampanel dose evaluated (12 mg/day) increased lamotrigine clearance by less than 10%. An effect of this magnitude is not considered to be clinically relevant.
Pregabalin
In 12 patients with partial-onset seizures receiving combination lamotrigine (mean lamotrigine dose 287.5 mg/day, range 100 to 600 mg/day) and pregabalin 600 mg/day (200 mg three times daily) therapy, steady-state trough plasma concentrations of lamotrigine were not affected by pregabalin. The pharmacokinetics of pregabalin when co-administered with lamotrigine in this study appeared similar to historical values for pregabalin in healthy volunteers.
Topiramate
In three studies in patients with epilepsy (n = 52), topiramate (dose range of topiramate in the 2 studies where this was recorded was 75 to 800 mg/day) resulted in no change in plasma concentrations of lamotrigine. Administration of lamotrigine resulted in a 15% increase in plasma concentrations of topiramate.
Valproic Acid
Valproic acid reduces the plasma clearance and prolongs the elimination half-life of lamotrigine (see 10 CLINICAL PHARMACOLOGY). When lamotrigine was administered to 18 healthy volunteers already receiving valproic acid, a modest decrease (25% on average) in the trough steady-state valproic acid plasma concentrations was observed over a 3-week period, followed by stabilization. However, the addition of lamotrigine did not affect the plasma concentration of valproic acid in patients receiving AEDs that induce lamotrigine glucuronidation in combination with valproic acid. See also 7 WARNINGS AND PRECAUTIONS, Skin-related events.
Zonisamide (not available in Canada)
In a study of 18 patients with epilepsy, coadministration of zonisamide (200 to 400 mg/day) with lamotrigine (150 to 500 mg/day) for 35 days had no significant effect on the pharmacokinetics of lamotrigine. Although the effects of lamotrigine on pharmacokinetics of zonisamide have not been studied, two post-marketing cases have reported zonisamide toxicity when lamotrigine was administered (zonisamide dose: 600 to 800 mg daily; lamotrigine dose: 400 mg daily). In both cases, positive dechallenge and rechallenge were observed.
Other Drug Interactions:
Acetaminophen (Paracetamol)
In a study in healthy volunteers, paracetamol 1 g (four times daily for 4 days) reduced the plasma AUC and Css,min of lamotrigine by an average of 20% and 25%, respectively. The formation clearance of lamotrigine glucuronides was increased by 45%. Rarely, cases of seizures / drug inefficiency have been reported.
Aripiprazole
In a study of 18 adult patients with bipolar I disorder, receiving an established regimen of lamotrigine (≥ 100 mg/day), doses of aripiprazole were increased from 10 mg/day to a target of 30 mg/day over a 7 day period and continued once daily for a further 7 days. An average reduction of approximately 10% in Cmax and AUC of lamotrigine was observed. An effect of this magnitude is not expected to be of clinical consequence.
Atazanavir/ritonavir
In a study of 21 healthy adult volunteers, atazanavir/ritonavir combination (300 mg/100 mg) reduced the plasma AUC, Cmax and elimination half-life of lamotrigine (single 100 mg dose) by an average of 32%, 6% and 27%, respectively. However, atazanavir alone did not induce lamotrigine glucuronidation (did not change pharmacokinetics of lamotrigine) to a clinically significant extent.
To initiate lamotrigine in patients already on the combination therapy of atazanavir/ritonavir, dose titration should follow the recommended guidelines based on whether lamotrigine is added to valproate (an inhibitor of lamotrigine glucuronidation), or to an inducer of lamotrigine glucuronidation, or whether lamotrigine is added in the absence of valproate or an inducer of lamotrigine glucuronidation (see 4 DOSAGE AND ADMINISTRATION, Table 1).
To initiate atazanavir/ritonavir in patients already on maintenance doses of lamotrigine, the lamotrigine dose may need to be increased if another glucuronidation inducer is taken, but its dose may remain unchanged in the absence of another inducer. The lamotrigine dose needs to be decreased if atazanavir/ritonavir are discontinued.
Lopinavir/ritonavir
In a study in healthy volunteers, lopinavir/ritonavir approximately halved the plasma concentrations of lamotrigine. At least 14 out of 22 healthy adult volunteers reported diarrhea and 5 out of 22 subjects reported rash following the addition of lopinavir/ ritonavir (400 mg/100 mg b.i.d.) to lamotrigine (up to 200 mg b.i.d.), compared to 1 out of 24 reporting diarrhea or rash, when lamotrigine was administered alone (up to 100 mg b.i.d.). Diarrhea is a common adverse event reported for lopinavir/ritonavir. The titration of lamotrigine in this study was rapid, which is a known risk factor for the development of a rash. The rashes necessitated the discontinuation of the medications. One subject also discontinued the medications due to elevated AST and ALT levels. Caution is advised for the co-administration of lopinavir/ritonavir with lamotrigine. In patients receiving concomitant therapy with lopinavir/ritonavir, the treatment regimen recommended for concomitant medications that induce lamotrigine glucuronidation (without VPA) should be used (see 4 DOSAGE AND ADMINISTRATION, Table 1).
Olanzapine
The AUC and Cmax of lamotrigine was reduced on average by 24% and 20%, respectively, following the addition of olanzapine (15 mg once daily) to lamotrigine (200 mg once daily) in healthy male volunteers (n = 16) compared to healthy male volunteers receiving lamotrigine alone (n = 12). This reduction in lamotrigine plasma concentrations is not expected to be clinically relevant.
Organic Cationic Transporter 2 (OCT 2)
Lamotrigine is an inhibitor of renal tubular secretion via OCT 2 proteins. This may result in increased plasma levels of certain drugs that are substantially excreted via this route. Co-administration of lamotrigine with OCT 2 substrates (i.e. procainamide and metformin) with a narrow therapeutic index is not recommended.
In vitro assessment of the effect of lamotrigine at OCT 2 demonstrate that lamotrigine, but not the N(2)-glucuronide metabolite, is an inhibitor of OCT 2 at potentially clinically relevant concentrations, with an IC50 value of 53.8 mcM.
Oral Contraceptives
Effect of Oral Contraceptives on Lamotrigine
In a study in 16 female volunteers, an oral contraceptive preparation containing 30 mcg ethinylestradiol and 150 mcg levonorgestrel increased the apparent clearance of lamotrigine (300 mg/day) by approximately 2-fold with a mean decrease in AUC of 52% and in Cmax of 39%. In this study, trough serum lamotrigine concentrations gradually increased and were approximately 2-fold higher on average at the end of the week of the inactive preparation compared to trough lamotrigine concentrations at the end of the active hormone cycle.
Gradual transient increases in lamotrigine levels will occur during the week of no active hormone preparation (pill-free week) for women not also taking a drug that increases the clearance of lamotrigine (carbamazepine, phenytoin, phenobarbital, primidone, or rifampin). The increase in lamotrigine levels will be greater if the dose of lamotrigine is increased in the few days before or during the pill-free week.
There have been post marketing reports of breakthrough seizures in women taking lamotrigine and hormonal contraceptives. Dosage adjustments will be necessary in most cases for women receiving oral contraceptive preparations (see 4.2 Recommended Dose and Dosage Adjustment, Starting Lamotrigine in Women Taking Oral Contraceptives and 8.5 Post-Market Adverse Reactions).
Effect of Lamotrigine on Oral Contraceptives
Co-administration of lamotrigine (300 mg/day) in 16 female volunteers did not affect the pharmacokinetics of the ethinylestradiol component of an oral contraceptive preparation containing 30 mcg ethinylestradiol and 150 mcg levonorgestrel. There was a mean decrease in the AUC and Cmax of the levonorgestrel component of 19% and 12%, respectively. Measurement of serum progesterone indicated that there was no hormonal evidence of ovulation in any of the 16 volunteers, although measurement of serum FSH, LH, and estradiol indicated that there was some loss of suppression of the hypothalamic-pituitary-ovarian axis.
The effects of doses of lamotrigine other than 300 mg/day have not been studied and studies with other female hormonal preparations (including progesterone/progesterone-containing HRT) have not been conducted.
The clinical significance of the observed hormonal changes on ovulatory activity is unknown. However, the possibility of decreased contraceptive efficacy in some patients cannot be excluded. Therefore, patients should be instructed to promptly report changes in their menstrual pattern (e.g., break-through bleeding).
Interactions with Other Hormonal Contraceptives or Hormone Replacement Therapy
The effect of other hormonal contraceptive preparations or estrogen-containing therapies, including hormone replacement therapy (HRT) on the pharmacokinetics of lamotrigine has not been evaluated, although the effect may be similar to oral contraceptive preparations. There have been reports of a possible interaction with estrogen HRTs which could lead to decreased efficacy of lamotrigine. Therefore, close clinical monitoring and similar dosage adjustments as for oral contraceptives may be necessary (see 4.2 Recommended Dose and Dosage Adjustment, Starting Lamotrigine in Women Taking Oral Contraceptives and 8.5 Post-Market Adverse Reactions).
Rifampin
In a study in 10 male volunteers, rifampin (600 mg/day for 5 days) significantly increased the apparent clearance of a single 25 mg dose of lamotrigine by approximately 2-fold (AUC decreased by approximately 40%). For patients taking rifampin with lamotrigine, follow the titration schedule for concomitant medications that induce lamotrigine glucuronidation (without VPA) (see 4 DOSAGE AND ADMINISTRATION, Table 1).
Risperidone
Following the co-administration of 2 mg risperidone with lamotrigine (up to 400 mg daily), 12 out of the 14 healthy adult volunteers reported somnolence compared to 1 out of 20 when risperidone was given alone, and 0 out of 20 when lamotrigine was administered alone.
Drugs Depressing Cardiac Conduction
See 7 WARNINGS AND PRECAUTIONS, Cardiovascular, Cardiac Rhythm Conduction Abnormalities.
9.6 Drug-Herb Interactions
Interactions with herbal products have not been established.
9.7 Drug-Laboratory Test Interactions
Lamotrigine has been reported to interfere with the assay used in some rapid urine drug screens, which can result in false positive readings, particularly for phencyclidine (PCP). A more specific alternative chemical method should be used to confirm a positive result.
10 CLINICAL PHARMACOLOGY
10.1 Mechanism of Action
Lamotrigine is a drug of the phenyltriazine class chemically unrelated to existing antiepileptic drugs (AEDs).
Lamotrigine is thought to act at voltage-sensitive sodium channels to stabilize neuronal membranes and inhibit the release of excitatory amino acid neurotransmitters (e.g., glutamate, aspartate) that are thought to play a role in the generation and spread of epileptic seizures.
10.2 Pharmacodynamics
In vitro studies show that lamotrigine exhibits Class IB antiarrhythmic activity at therapeutically relevant concentrations. It inhibits human cardiac sodium channels with rapid onset and offset kinetics and strong voltage dependence, consistent with other Class IB antiarrhythmic agents. At therapeutic doses, lamotrigine did not slow ventricular conduction (widen QRS) in healthy individuals in a thorough QT study; however, in patients with clinically important structural or functional heart disease lamotrigine could potentially slow ventricular conduction by prolonging QRS duration and inducing proarrhythmia (see 7 WARNINGS AND PRECAUTIONS, Cardiovascular, Cardiac Rhythm Conduction Abnormalities).
10.3 Pharmacokinetics
Lamotrigine exhibits linear pharmacokinetics (PK) across doses of 50 to 400 mg. It is metabolised hepatically to non-pharmacologically active metabolites. The PK of healthy individuals is similar to that of patients (see Table 13).
Table 12 Summary of Lamotrigine Pharmacokinetic Parameters in Healthy Adults Population
| PK parameters in healthy adults | Cmax (mg/L)1 | Tmax (h)2 | t½ (h)2 | AUC0-∞ (mg/L*h)1 | CL/F (mL/min/kg)2 | Vd/F (L/kg) |
|---|---|---|---|---|---|---|
| Single dose mean | 2.3 | 2.2 | 32.8 | 95.9 | 0.44 | 1.07 |
| Multiple dose mean | 7.1 | 1.7 | 25.4 | 71.0 | 0.58 | 1.09 |
1 Average derived from several studies
2 For a dose of 150 mg (single or twice daily)
Absorption
Adults: Lamotrigine is rapidly and completely absorbed following oral administration, reaching peak plasma concentrations 1.4 to 4.8 hours (Tmax) post-dosing. When administered with food, the rate of absorption is slightly reduced, but the extent remains unchanged. Following single lamotrigine doses of 50 to 400 mg, peak plasma concentration (Cmax = 0.6 to 4.6 mcg/mL) and the area under the plasma concentration-versus-time curve (AUC = 29.9 to 211 h.mcg/mL) increase linearly with dose. The time-to-peak concentration, elimination half-life (t½) and volume of distribution (Vd/F) are independent of dose. The t½ averages 33 hours after single doses and Vd/F ranges from 0.9 to 1.4 L/kg. Following repeated dosing in healthy volunteers for 14 days, the t½ decreased by an average of 26% (mean steady state t½ of 26.4 hours) and plasma clearance increased by an average of 33%. In a single-dose study where healthy volunteers were administered both oral and intravenous doses of lamotrigine, the absolute bioavailability of oral lamotrigine was 98%.
Distribution
Lamotrigine is approximately 55% bound to human plasma proteins. This binding is unaffected by therapeutic concentrations of phenytoin, phenobarbital or valproic acid. Lamotrigine does not displace other antiepileptic drugs (carbamazepine, phenytoin, phenobarbital) from protein binding sites.
Metabolism
Lamotrigine is metabolized predominantly in the liver by glucuronic acid conjugation. The major metabolite is an inactive 2-N-glucuronide conjugate that can be hydrolyzed by β-glucuronidase.
Elimination
Approximately 70% of an oral lamotrigine dose is recovered in urine as this metabolite.
Special Populations and Conditions
- Pediatrics: Lamotrigine was rapidly absorbed in children, with a Tmax ranging from 1 to 6 hours. The mean Vd/F of lamotrigine in children aged 5 to 11 years (1.3 to 1.4 L/kg) was similar to those seen in adults (0.9 to 1.4 L/kg) but was larger in younger children (1.8 to 2.3 L/kg). As with adults, the elimination of lamotrigine in pediatric patients was similarly affected by concomitant AEDs. While the CL/F was higher and t½ was shorter in younger children than in older children, the mean CL/F was higher and mean t½ was shorter in both pediatric groups than in adults. Population analysis results showed that the estimated apparent plasma clearances in patients aged 13 to 18 years were similar to those found in adult patients.
- Geriatrics: Results of a population pharmacokinetic analysis, based on individual trials in which both adult (n = 138) and elderly (n = 13) patients with epilepsy were enrolled, indicated that the clearance of lamotrigine in elderly patients did not change to a clinically relevant extent. After single doses, apparent clearance was lower in the elderly by 12% (31 mL/min at age 70 vs 35 mL/min at age 20). After 48 weeks of treatment, the difference in clearance was 10% (37 mL/min at age 70 vs 41 mL/min at age 20). In addition, the pharmacokinetics of lamotrigine were studied in 12 healthy elderly volunteers who each received a single oral dose of 150 mg. The mean clearance in the elderly (0.39 mL/min) lies within the range of mean clearance values (0.31 to 0.65 mL/min) obtained in 9 studies with non-elderly adults after single doses of 30 to 450 mg (see 4.2 Recommended Dose and Dosage Adjustment and 8 ADVERSE REACTIONS).
Hepatic Insufficiency: A single dose pharmacokinetic study was performed in 24 subjects with hepatic impairment (n = 12 mild/Grade A; n = 5 moderate/Grade B and n = 7 severe/Grade C), versus 12 healthy controls. For the moderate and severe subgroups, the mean values for AUC and plasma half-life were increased approximately 2-fold and 3-fold respectively over control values, with clearance decreased proportionately. For the mild group, while mean values were not statistically different from those of controls, a subgroup of 1 to 4 subjects (dependant on pharmacokinetic parameter examined) showed abnormal individual values which were in the range of the moderately impaired subjects (see 4.2 Recommended Dose and Dosage Adjustment and 7 WARNINGS AND PRECAUTIONS).
- Gilbert's Syndrome: Gilbert's syndrome (idiopathic unconjugated hyperbilirubinemia) does not appear to affect the pharmacokinetic profile of lamotrigine.
Renal Insufficiency: The pharmacokinetics of a single oral dose of lamotrigine (100 mg) were evaluated in 12 individuals with chronic renal failure (with mean creatinine clearance of 13 mL/min) who were not receiving other antiepileptic drugs. In this study, the elimination half-life of unchanged lamotrigine was prolonged (by an average of 63%) relative to individuals with normal renal function (see 7 WARNINGS AND PRECAUTIONS, Renal and 4.2 Recommended Dose and Dosage Adjustment).
- Hemodialysis: In six hemodialysis patients, the elimination half-life of unchanged lamotrigine was doubled off dialysis, and reduced by 50% on dialysis, relative to individuals with normal renal function.
Concomitant Antiepileptic Drugs
In patients with epilepsy, concomitant administration of lamotrigine and AEDs that induce lamotrigine glucuronidation (phenytoin, carbamazepine, primidone or phenobarbital) decreases the mean lamotrigine t½ to 13 hours. Concomitant administration of lamotrigine with valproic acid significantly increases t½ and decreases the clearance of lamotrigine, whereas concomitant administration of lamotrigine with valproic acid plus AEDs that induce lamotrigine glucuronidation can prolong t½ up to approximately 27 hours. The key lamotrigine parameters for adult patients and healthy volunteers are summarized in Table 13, and for pediatric patients in Table 14.
Table 13 Mean Pharmacokinetic Parameters in Adult Patients with Epilepsy or Healthy Volunteers
| Lamotrigine Administered | Healthy Young Volunteers | Patients with Epilepsy | ||||
| Lamotrigine | Lamotrigine + Valproic Acid2 | Lamotrigine + AEDs that induce lamotrigine glucuronidation | Lamotrigine + Valproic Acid | Lamotrigine + AEDs that induce lamotrigine glucuronidation + Valproic Acid | ||
Tmax (hrs) | Single Dose | 2.2 (0.25-12.0)1 | 1.8 (1.0-4.0) | 2.3 (0.5-5.0) | 4.8 (1.8-8.4) | 3.8 (1.0-10.0) |
| Multiple Dose | 1.7 (0.5-4.0) | 1.9 (0.5-3.5) | 2.0 (0.75-5.93) | ND | ND | |
t½ (hr) | Single Dose | 32.8 (14.0-103.0) | 48.3 (31.5-88.6) | 14.4 (6.4-30.4) | 58.8 (30.5-88.8) | 27.2 (11.2-51.6) |
| Multiple Dose | 25.4 (11.6-61.6) | 70.3 (41.9-113.5) | 12.6 (7.5-23.1) | ND | ND | |
| Plasma Clearance (mL/min/ kg) | Single Dose | 0.44 (0.12-1.10) | 0.30 (0.14-0.42) | 1.10 (0.51-2.22) | 0.28 (0.16-0.40) | 0.53 (0.27-1.04) |
| Multiple Dose | 0.58 (0.25-1.15) | 0.18 (0.12-0.33) | 1.21 (0.66-1.82) | ND | ND | |
ND = Not done
| ||||||
Table 14 Mean Pharmacokinetic Parameters in Pediatric Patients with Epilepsy
| Pediatric Study Population | Number of Subjects | Tmax (h) | t½ (h) | CL/F (mL/min/kg) |
| Pediatric Study Population | Number of Subjects | Tmax (h) | t½ (h) | CL/F (mL/min/kg) |
| Ages 10 months to 5.3 years | ||||
| Patients taking AEDs that induce lamotrigine glucuronidation | 10 | 3.0 (1.0-5.9) | 7.7 (5.7-11.4) | 3.62 (2.44-5.28) |
| Patients taking AEDs with no known effect on drug- metabolizing enzymes | 7 | 5.2 (2.9-6.1) | 19.0 (12.9-27.1) | 1.2 (0.75-2.42) |
| Patients taking VPA only | 8 | 2.9 (1.0-6.0) | 44.9 (29.5-52.5) | 0.47 (0.23-0.77) |
| Ages 5 to 11 years | ||||
| Patients taking AEDs that induce lamotrigine glucuronidation | 7 | 1.6 (1.0-3.0) | 7.0 (3.8-9.8) | 2.54 (1.35-5.58) |
| Patients taking AEDs that induce lamotrigine glucuronidation plus VPA | 8 | 3.3 (1.0-6.4) | 19.1 (7.0-31.2) | 0.89 (0.39-1.93) |
| Patients taking VPA only* | 3 | 4.5 (3.0-6.0) | 55.4 (24.3-73.7) | 0.31 (0.20-0.54) |
| Ages 13 to 18 years | ||||
| Patients taking AEDs that induce lamotrigine glucuronidation | 11 | † | † | 1.3 |
| Patients taking AEDs that induce lamotrigine glucuronidation plus VPA | 8 | † | † | 0.5 |
| Patients taking VPA only | 4 | † | † | 0.3 |
VPA = valproic acid * Two subjects were included in the calculation for mean tmax † Parameter not estimated. | ||||
Oxcarbazepine, gabapentin, lacosamide, levetiracetam, perampanel, pregabalin, felbamate, zonisamide and topiramate did not affect the plasma concentrations of lamotrigine (see 9.4 Drug-Drug Interactions, Antiepileptic Drugs (AEDs)).
Other Drug Interactions: Chronic administration of acetaminophen was shown to slightly decrease the t½ and increase the clearance of a single dose of lamotrigine. Oral contraceptives and rifampin have also been shown to increase the apparent clearance of lamotrigine (see 9 DRUG INTERACTIONS). Co-administration of olanzapine did not have a clinically relevant effect on lamotrigine pharmacokinetics (see 9 DRUG INTERACTIONS).
11 STORAGE, STABILITY AND DISPOSAL
Store at controlled room temperature (15°C to 30°C) in tight containers, in a dry place and protected from light.
Keep out of reach and sight of children.
12 SPECIAL HANDLING INSTRUCTIONS
There are no special handling instructions.
PART II: SCIENTIFIC INFORMATION
13 PHARMACEUTICAL INFORMATION
Drug Substance
Proper name: Lamotrigine
Chemical name: 1) 1,2,4-Triazine-3,5-diamine,6-(2,3-dichlorophenyl)- [Chem. Abstr.]
- 2) 1,2,4-Triazine-3,5-diamine,6-(2,3-dichlorophenyl)-[USAN]
Molecular formula and molecular mass: C9H7CI2N5 and 256.09 g/mol
Structural formula:
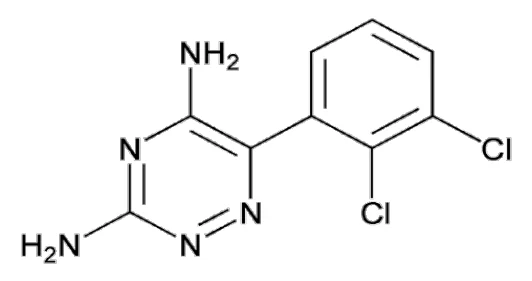
Physicochemical properties: Lamotrigine is a white to off-white powder that is non-hydroscopic and has moderate surface area and porosity. It has a melting point between 215 to 219°C, the pH of a saturated water solution is 6.88, and the pKa at 25°C is 5.7. It is soluble in dimethylformamide, slightly soluble in acetone, and very slightly soluble in water (0.153 g/L).
14 CLINICAL TRIALS
14.2 Study Results
In adult placebo-controlled clinical studies, lamotrigine has been shown to be effective in reducing seizure frequency and the number of days with seizures when added to existing antiepileptic drug therapy in adult patients with partial seizures, with or without generalized tonic-clonic seizures, that are not satisfactorily controlled.
The effectiveness of lamotrigine adjunctive therapy has also been shown in pediatric and adult patients with Lennox-Gastaut syndrome. A significant reduction in major motor seizures, drop attacks, and tonic-clonic seizures were seen following lamotrigine treatment compared with placebo treated patients. Improvements in cognitive skills (speech, nonverbal communication, alertness, attention, intellectual capacity), behaviour, and fine co-ordination have been seen with lamotrigine treatment in these patients.
Studies have also been conducted using lamotrigine monotherapy in adult patients (n = 443) newly diagnosed with epilepsy (partial seizures, with or without secondary generalization or primary generalized tonic clonic). Results have shown comparable efficacy (time to first seizure, seizure frequency, percentage of patients seizure-free) with fewer side effects than currently approved therapies.
Clinical trials have also demonstrated that adult patients (any seizure type) can be converted to lamotrigine monotherapy from polytherapy with significant numbers of patients maintaining or improving seizure control. Efficacy was maintained during long-term treatment (up to 152 weeks).
A 24 week monotherapy trial was conducted in elderly newly diagnosed patients (102 patients received lamotrigine and 48 received carbamazepine). The findings indicate comparable efficacy and demonstrate that lamotrigine was well tolerated in the elderly. However, the small and unbalanced number of patients in the study precludes any firm conclusions on the relative safety of the two drugs.
14.3 Comparative Bioavailability Studies
A blinded, randomized, two-treatment, two-period, single oral dose (1 x 150 mg), crossover comparative bioavailability study of APO-LAMOTRIGINE tablets 150 mg (Apotex Inc.) and LAMICTAL® tablets 150 mg (Glaxo Wellcome Inc.), was conducted in healthy, adult male subjects under fasting conditions. Comparative bioavailability data from 18 subjects that were included in the statistical analysis are presented in the following table:
Table 15 a SUMMARY TABLE OF THE COMPARATIVE BIOAVAILABILITY DATA
Lamotrigine (1 x 150 mg) Geometric Mean Arithmetic Mean (CV %) | ||||
| Parameter | Test1 | Reference2 | % Ratio of Geometric Means | 95% Confidence Interval |
AUC0-72h (ng·h/mL) | 64344 65595 (21) | 62630 64032 (22) | 102.7 | 98.9 – 106.6 |
AUCI (ng·h/mL) | 82702 90561 (61) | 83533 100484 (94) | 99.0 | 89.2 – 109.8 |
Cmax (ng/mL) | 1961 1972 (11) | 2037 2071 (18) | 96.3 | 90.3 – 102.7 |
Tmax3 (h) | 2.07 (47) | 1.52 (55) | ||
T½3 (h) | 34.2 (67) | 40.1 (107) | ||
1 APO-LAMOTRIGINE (lamotrigine) tablets, 150 mg (Apotex Inc.)
2 LAMICTAL® (lamotrigine) tablets, 150 mg (Glaxo Wellcome Inc., Canada)
3 Expressed as the arithmetic mean (CV %) only
A blinded, randomized, two-treatment, two-period, single oral dose (1 x 150 mg), crossover comparative bioavailability study of APO-LAMOTRIGINE tablets 150 mg (Apotex Inc.) and LAMICTAL® tablets 150 mg (Glaxo Wellcome Inc.), was conducted in healthy, adult male subjects under fed conditions. Comparative bioavailability data from 24 subjects that were included in the statistical analysis are presented in the following table:
Table 15 b SUMMARY TABLE OF THE COMPARATIVE BIOAVAILABILITY DATA
Lamotrigine (1 x 150 mg) Geometric Mean Arithmetic Mean (CV %) | ||||
| Parameter | Test1 | Reference2 | % Ratio of Geometric Means | 95% Confidence Interval |
AUC0-72h (ng·h/mL) | 57240 58343 (21) | 55105 56073 (20) | 103.9 | 101.0 – 106.8 |
AUCI (ng·h/mL) | 73939 78732 (43) | 71396 76631 (45) | 103.5 | 99.0 – 108.2 |
Cmax (ng/mL) | 1671 1679 (10) | 1638 1642 (8) | 102.1 | 99.7 – 104.5 |
Tmax3 (h) | 3.41 (26) | 3.56 (19) | ||
T½3 (h) | 32.9 (39) | 33.5 (47) | ||
1 APO-LAMOTRIGINE (lamotrigine) tablets, 150 mg (Apotex Inc.)
2 LAMICTAL® (lamotrigine) tablets, 150 mg (Glaxo Wellcome Inc., Canada)
3 Expressed as the arithmetic mean (CV %) only
15 MICROBIOLOGY
No microbiological information is required for this drug product.
16 NON-CLINICAL TOXICOLOGY
In vivo studies
In in vivo studies in animal models, lamotrigine has an antiepileptic profile suggesting utility in the treatment of partial seizures and generalized tonic-clonic seizures. Lamotrigine was effective in the maximal electroshock (MES), maximum pentylenetetrazol, electrically evoked after discharge (EEAD) tests and in visually evoked after discharge (VEAD) tests. In mice and rats, lamotrigine has a longer duration of action than phenytoin, carbamazepine, diazepam or valproate. Lamotrigine's potency is similar to that of phenytoin (mouse), phenobarbital (rat), carbamazepine (rat) and diazepam (mouse) (see Table 16).
Table 16 Potency and Duration of Lamotrigine Following Maximal Electroshock-Induced Seizures
| Drug | ED50 for Abolition of Hind Leg Extension (mg/kg p.o.) | Duration Maintenance of Peak Activity (hours) |
| Mouse | ||
| Rat | Mouse | |
| Rat | ||
Lamotrigine Phenytoin Phenobarbital Carbamazepine Valproate Diazepam | 2.6 - 3.8 3.5 9.1 6.9 332.4 3.2 | |
1.9 - 3.3 19.7 4.7 2.5 238 16.9 | 1 – 8 8 1 1 0.25 1 | |
1 – 8 1 1 0.25 1 1 | ||
In single-dose mouse and rat studies, the anticonvulsant ED50s of orally administered lamotrigine ranged from 1.9 to 3.8 mg/kg. Signs of CNS toxicity did not occur until high multiples of the lamotrigine ED50s were reached and consisted of ataxia and tremors (at 140 mg/kg), and convulsions (at 300 and 675 mg/kg in mice and rats, respectively). In multiple-dose studies in mice and rats, the anticonvulsant ED50s were unchanged. In mice, lamotrigine was well tolerated at chronic doses up to 30 mg/kg/day. In rats, convulsions possibly related to drug administration were rarely observed (in no more than 1 of 46 to 49 animals per dose group) and did not occur until week 24 of chronic oral dosing with 15 mg/kg/day.
Preclinical Pharmacokinetics
Lamotrigine was found to accumulate in the kidney of the male rat, bind to melanin-containing ocular tissue of the pigmented rat and cynomolgus monkey, and prolong gastric emptying time in rats. In dogs, lamotrigine was extensively metabolized to a 2-N-methyl metabolite which produced dose-dependent prolongations of the P-R interval and QRS duration in ECG tracings in this species. Only trace amounts of this metabolite (< 0.6% of lamotrigine dose) were found in human urine. Clinical studies showed no evidence in humans for manifestations of these preclinical observations regarding accumulation in the kidney, melanin binding, gastric emptying, or clinically relevant cardiac effects.
In vitro Studies
In vitro pharmacological studies suggest that lamotrigine acts at voltage-sensitive sodium channels to stabilize neuronal membranes and inhibit the release of excitatory amino acid neurotransmitters (e.g., glutamate, aspartate) that are thought to play a role in the generation and spread of epileptic seizures.
General Toxicology:
- Acute Toxicity Single-dose lethality values were calculated in male and female mice and rats receiving lamotrigine by the oral and intravenous routes of administration. The calculated LD50 values are listed in Table 17.
Table 17 Acute Toxicity Studies
| Route | LD50 Dose (mg/kg) | |||||||||
| Mouse | Rat | |||||||||
| Male | Female | Male | Female | |||||||
| Oral | 245 | 292 | 205 | 163 | ||||||
| I.V. | 141 | 134 | 107 | 112 | ||||||
The lowest doses (mg/kg) at which any deaths occurred were 300 (oral) and 125 (I.V.) in mice and 140 (oral) and 100 (I.V.) in rats. Deaths were seen as early as 1 minute following I.V. dosing and 30 minutes following oral dosing. The most severe sign noted was clonic convulsions (rats only). Other signs, including tremors, ataxia, hypoactivity, decreased respiration, and hypothermia were also observed. Survivors generally recovered within 24 hours, but hypoactivity lasted for several days in some animals.
Long-Term Toxicity Subacute to subchronic (14 to 30 days) studies were conducted in rats (oral and intravenous), marmosets (oral) and cynomolgus monkeys (intravenous).
Effects seen in rats which were considered to be consistently associated with oral lamotrigine administration included specific nephropathy (males, 1 mg/kg/day), increased weight of stomach contents (6.25 mg/kg/day), increased water consumption and urine output (10 mg/kg/day), reduced weight gain and food consumption (22.5 mg/kg/day), and convulsions (50 mg/kg/day).
Marmosets were given either single daily lamotrigine doses of 10 to 100 mg/kg/day or 3 daily doses ranging from 10 to 50 mg/kg/dose. The following effects were observed at the following lowest doses given: slight decreases in WBC, RBC and related values (100 mg/kg/day or 22.5 mg/kg/dose t.i.d.); post-dose incoordination, slight body weight loss, decreased food consumption (50 mg/kg/day or 22.5 mg/kg/dose t.i.d.); post-dose salivation and vomiting (10 mg/kg/day or 22.5 mg/kg/dose t.i.d.). Blood, brain and liver folate levels were not affected.
In a 14-day intravenous study in cynomolgus monkeys, daily lamotrigine doses ranged from 5 to 20 mg/kg. The following effects were observed (shortly after dosing) at the following lowest doses given: ataxia, vomiting, and decreased food consumption (10 mg/kg); nystagmus (15 mg/kg); agitation, slight body weight loss (20 mg/kg).
In chronic oral toxicity studies, mice were given daily lamotrigine doses of up to 60 mg/kg for 90 days. Rats were given doses of up to 30 mg/kg/day for 90 days, up to 25 mg/kg/day for 6 months, and up to 15 mg/kg/day for one year. The only effect seen in mice was increased stomach content weight, likely related to delayed gastric emptying (30 and 60 mg/kg/day). The most prominent drug-related effects in rats were renal histopathological changes, seen at all dose levels; other effects seen were similar to those documented in the subacute and subchronic rat studies. Other species were also evaluated by light microscopic examination of kidney sections from animals given lamotrigine and by in vitro studies of kidney cortex slice uptake of radiolabelled lamotrigine. The studies demonstrated that the renal effects seen are limited to male rats and represent exacerbation of spontaneous hyaline droplet changes related to the renal proximal tubular handling of α2u-globulin. This globulin is a specific protein synthesized by the liver in male rats only. The hyaline droplets are secondary lysosomes and contain α2u-globulin. Lamotrigine is also accumulated in the renal proximal tubular epithelium in the form of rectilinear and crystalline inclusions which likely contain both α2u-globulin and lamotrigine. Time-and-dose dependent loading of these cells leads to cellular degeneration and eventual regeneration. Changes are consistent with those seen in "light hydrocarbon nephropathy," a male-rat-specific condition, which is reversible following termination of treatment and has no human counterpart.
Cynomolgus monkeys were treated with daily oral lamotrigine doses of up to 20 mg/kg in 13-week, 26-week, and 52-week studies. Effects noted were limited to animals given 20 mg/kg/day and included postdose ataxia, lethargy, trembling, locomotor incoordination and convulsions in some animals in the 26-week study. A reduced rate of body weight gain and transient weight loss was seen at doses as low as 5 mg/kg/day, but only in the 52-week study.
Carcinogenicity: There was no evidence of carcinogenicity in mice treated orally with lamotrigine (10 to 30 mg/kg/day) for up to 106 weeks. Lamotrigine was not carcinogenic in two rat studies where animals received doses of 1 to 10 mg/kg/day for up to 104 weeks (females) or 112 weeks (males). In both studies, survival was not affected by treatment.
Genotoxicity: In vitro, lamotrigine was not mutagenic in microbial (Ames) or mammalian (mouse lymphoma) mutagenicity tests with or without metabolic activation. Lamotrigine had no effect on the incidence of chromosomal abnormalities in cultured human lymphocytes exposed to concentrations of up to 1000 mcg/mL in the presence or absence of S9 metabolic activation. Concentrations of 500 and 1000 mcg/mL without activation were cytotoxic.
In vivo, there was no increase in the incidence of chromosomal abnormalities in bone marrow cells of rats given doses of lamotrigine of up to 200 mg/kg.
Reproduction and Developmental Toxicology: No evidence of teratogenicity was observed in mice, rats, and rabbits given oral doses of lamotrigine at up to 14, 4, and 4 times, respectively, the currently recommended upper human maintenance dose (500 mg/day or 7 mg/kg/day). This was true when lamotrigine was given during the period of major organogenesis or was started prior to and continued throughout the period of organogenesis. In these same oral dosing studies maternal toxicity and secondary fetal toxicity, resulting in reduced fetal weight and/or delayed ossification were seen. Teratology studies were also conducted using bolus intravenous (I.V.) administration of the isethionate salt of lamotrigine in multiples of the projected human oral dose. Intravenous lamotrigine resulted in convulsions or impaired coordination in rat and rabbit dams at 30 mg/kg and 15 mg/kg, respectively. The 30 mg/kg dose also produced an increased incidence of intrauterine death without signs of teratogenicity in rats only.
When rats were dosed prior to and during mating, and throughout gestation and lactation at daily oral doses of 5, 10, and 20 mg/kg, gestation was slightly longer in the dams allowed to deliver in the 20 mg/kg/group (22.0 ± 0.0 versus 21.5 ± 0.5 days in non-treated controls). These doses are approximately 1, 1.5, and 3 times the currently recommended upper human maintenance dose (500 mg/day or 7 mg/kg/day). In this same study, body weight gain and food consumption of the parent generation (F0) dams dosed at 20 mg/kg/day were less than the control dams and were indicative of maternal toxicity. There was no evidence of teratogenic effects in the litters of the dams designated for cesarean section. Effects secondary to maternal toxicity consisted of a decrease in mean fetal weight and length of 20 mg/kg pups; the incidence of two skeletal variants was increased and the incidence of one skeletal variant was decreased. When pregnant rats of the same strain were dosed only on days 15 to 20 of gestation at the same daily doses of 5, 10, and 20 mg/kg, more pronounced maternal toxicity, than noted in the previously described study at the same doses, was seen in dams given 10 and 20 mg/kg doses and consisted of dehydration, hypothermia, and decreased weight gain and food consumption. A smaller decrease in body weight gain was seen in the 5 mg/kg group. Gestation was prolonged in the 20 mg/kg group (22.6 vs. 22.0 days in non-treated controls) and secondary to maternal toxicity there were increased numbers of stillborn pups (partial to entire litters) in the 10 and 20 mg/kg groups and increased early neonatal mortality.
Even at maternally toxic levels leading to fetal death, there was no evidence of teratogenicity. Because animal reproduction studies are not always predictive of human response, this drug should be used during pregnancy only if clearly needed. Clinical data indicate that lamotrigine has no effect on blood folate concentrations in adults; however, the effects of lamotrigine on fetal blood folate levels in utero are unknown.
17 SUPPORTING PRODUCT MONOGRAPHS
- 1. LAMICTAL® [Tablets, 25 mg, 100 mg and 150 mg and Dispersible Tablets, 2 mg and 5 mg], submission control 291590, Product Monograph, GlaxoSmithKline Inc. (MAR 26, 2025)