


Product Monograph - Apo-Levothyroxine
RECENT MAJOR LABEL CHANGES
| 7 WARNINGS AND PRECAUTIONS, Monitoring and Laboratory Tests | 08/2024 |
TABLE OF CONTENTS
Sections or subsections that are not applicable at the time of authorization are not listed.
RECENT MAJOR LABEL CHANGES ......................................................................................... 2
TABLE OF CONTENTS ............................................................................................................... 2
PART I: HEALTH PROFESSIONAL INFORMATION .................................................................. 4
1 INDICATIONS ..................................................................................................................... 4
1.1 Pediatrics ................................................................................................................. 4
1.2 Geriatrics .................................................................................................................. 4
2 CONTRAINDICATIONS ...................................................................................................... 4
3 SERIOUS WARNINGS AND PRECAUTIONS BOX ........................................................... 5
4 DOSAGE AND ADMINISTRATION .................................................................................... 5
4.1 Dosing Considerations ............................................................................................. 5
4.2 Recommended Dose and Dosage Adjustment ........................................................ 6
4.4 Administration ........................................................................................................ 10
4.5 Missed Dose .......................................................................................................... 10
5 OVERDOSAGE ................................................................................................................. 10
6 DOSAGE FORMS, STRENGTHS, COMPOSITION AND PACKAGING .......................... 11
7 WARNINGS AND PRECAUTIONS ................................................................................... 13
7.1 Special Populations ................................................................................................ 17
7.1.1 Pregnant Women ................................................................................................... 17
7.1.2 Breast-feeding ........................................................................................................ 17
7.1.3 Pediatrics ............................................................................................................... 17
7.1.4 Geriatrics ................................................................................................................ 19
8 ADVERSE REACTIONS ................................................................................................... 19
8.1 Adverse Reaction Overview ................................................................................... 19
9 DRUG INTERACTIONS .................................................................................................... 20
9.2 Drug Interactions Overview .................................................................................... 20
9.3 Drug-Behavioural Interactions ................................................................................ 20
9.4 Drug-Drug Interactions ........................................................................................... 20
9.5 Drug-Food Interactions .......................................................................................... 25
9.6 Drug-Herb Interactions ........................................................................................... 25
9.7 Drug-Laboratory Test Interactions ......................................................................... 25
10 CLINICAL PHARMACOLOGY .......................................................................................... 26
10.1 Mechanism of Action .............................................................................................. 26
10.3 Pharmacokinetics ................................................................................................... 27
11 STORAGE, STABILITY AND DISPOSAL ........................................................................ 28
PART II: SCIENTIFIC INFORMATION ....................................................................................... 29
13 PHARMACEUTICAL INFORMATION .............................................................................. 29
14 CLINICAL TRIALS ............................................................................................................ 29
14.1 Trial Design and Study Demographics ................................................................... 29
14.2 Study Results ......................................................................................................... 31
14.3 Comparative Bioavailability Studies ....................................................................... 31
15 MICROBIOLOGY .............................................................................................................. 32
16 NON-CLINICAL TOXICOLOGY ........................................................................................ 32
17 SUPPORTING PRODUCT MONOGRAPHS ..................................................................... 33
PATIENT MEDICATION INFORMATION .................................................................................. 34
PART I: HEALTH PROFESSIONAL INFORMATION
1 INDICATIONS
APO-LEVOTHYROXINE (levothyroxine sodium) is indicated for:
Hypothyroidism
APO-LEVOTHYROXINE is indicated as a replacement or supplemental therapy in patients of any age with primary (thyroidal), secondary (pituitary), and tertiary (hypothalamic) hypothyroidism of any etiology, in any state (including pregnancy) except transient hypothyroidism during the recovery phase of subacute thyroiditis;
Pituitary Thyrotropin (Thyroid-stimulating hormone, TSH) Suppression
APO-LEVOTHYROXINE is indicated as an adjunct to surgery and radioactive iodine therapy in the management of thyrotropin-dependent well-differentiated papillary or follicular carcinoma of the thyroid.
1.1 Pediatrics
Pediatrics (<18 years of age including neonates): Based on the data submitted and reviewed by Health Canada, the safety and efficacy of levothyroxine sodium in pediatric patients has been established. Therefore, Health Canada has authorized an indication for pediatric use (see 4 DOSAGE AND ADMINISTRATION, 4.2 Recommended Dose and Dosage Adjustment, Pediatric Dosage).
1.2 Geriatrics
Geriatrics (≥65 years of age): APO-LEVOTHYROXINE is approved for use in the geriatric population. However, experience suggests that use in the geriatric population is associated with differences in safety or effectiveness and dosing precautions apply (see 4 DOSAGE AND ADMINISTRATION, 4.2 Recommended Dose and Dosage Adjustment, 7 WARNINGS AND PRECAUTIONS, 7.1 Special Populations, 7.1.4 Geriatrics).
2 CONTRAINDICATIONS
APO-LEVOTHYROXINE is contraindicated in:
- Patients who are hypersensitive to this drug or to any ingredient in the formulation, including any non-medicinal ingredient, or component of the container. For a complete listing, see 6 DOSAGE FORMS, STRENGTHS, COMPOSITION AND PACKAGING.
- Patients with untreated subclinical thyrotoxicosis (suppressed serum TSH with normal L- triiodothyronine/liothyronine [T3] and L-thyroxine/levothyroxine [T4] levels) or overt thyrotoxicosis of any etiology.
- Patients with acute myocardial infarction, acute myocarditis, or acute pancarditis.
- Patients with uncorrected/untreated adrenal insufficiency, as thyroid hormones increase tissue demands for adrenocortical hormones and may thereby precipitate acute adrenal crisis by increasing the metabolic clearance of glucocorticoids (see 7 WARNINGS AND PRECAUTIONS, Immune Polyglandular Syndrome).
- Pregnant women being treated with drugs for hyperthyroidism, such as methimazole and propylthiouracil. Combination therapy of hyperthyroidism with levothyroxine and anti-thyroid agents is not indicated in pregnancy. (see 7 WARNINGS AND PRECAUTIONS, 7.1 Special Populations, 7.1.1 Pregnant Women).
3 SERIOUS WARNINGS AND PRECAUTIONS BOX
Serious Warnings and Precautions
| Thyroid hormones, including APO-LEVOTHYROXINE, either alone or with other therapeutic agents, should not be used for the treatment of obesity or for weight loss. In euthyroid patients, doses within the range of daily hormonal requirements are ineffective for weight reduction. Larger doses may produce serious or even life-threatening manifestations of toxicity, particularly when given in association with sympathomimetic amines such as those used for their anorectic effects. |
|---|
4 DOSAGE AND ADMINISTRATION
4.1 Dosing Considerations
The dosage and frequency of administration of APO-LEVOTHYROXINE is determined by the indication, and must in every case be individualized according to patient response and laboratory findings.
Unless bioequivalence has been demonstrated (see 14.3 Comparative Bioavailability Studies), levothyroxine sodium products from different manufacturers should not be used interchangeably unless retesting of the patient and re-titration of the dosage, as necessary, accompanies the product switch.
Hypothyroidism:
The goal of therapy for primary hypothyroidism is to achieve and maintain a clinical and biochemical euthyroid state with consequent resolution of hypothyroid signs and symptoms. The starting dose of APO-LEVOTHYROXINE, the frequency of dose titration, and the optimal full replacement dose must be individualized for every patient, and will be influenced by such factors as age, weight, cardiovascular status, presence of other illness, and the severity and duration of hypothyroid symptoms.
In patients with hypothyroidism resulting from pituitary or hypothalamic disease, the possibility of secondary adrenal insufficiency should be considered, and if present, treated with glucocorticoids prior to initiation of APO-LEVOTHYROXINE. The adequacy of levothyroxine sodium therapy should be assessed in these patients by measuring free T4 (FT4), which should be maintained in the upper half of the normal range, in addition to clinical assessment. Measurement of TSH is not a reliable indicator of response to therapy for this condition.
TSH Suppression in Thyroid Cancer:
The rationale for TSH suppression therapy is that a reduction in TSH secretion may decrease the growth and function of abnormal thyroid tissue. Exogenous thyroid hormone may inhibit recurrence of tumour growth and may produce regression of metastases from well-differentiated
(follicular and papillary) carcinoma of the thyroid. It is used as ancillary therapy of these conditions following surgery or radioactive iodine therapy. Medullary and anaplastic carcinoma of the thyroid is unresponsive to TSH suppression therapy.
No controlled studies have compared the various degrees of TSH suppression in the treatment of either benign or malignant thyroid nodular disease. Further, the effectiveness of TSH suppression for benign nodular disease is controversial.
The dose of APO-LEVOTHYROXINE used for TSH suppression should therefore be individualized by the nature of the disease, the patient being treated, and the desired clinical response, weighing the potential benefits of therapy against the risks of iatrogenic thyrotoxicosis. In general, APO-LEVOTHYROXINE should be given in the smallest dose that will achieve the desired clinical response.
Pediatric
Congenital or acquired hypothyroidism:
The APO-LEVOTHYROXINE pediatric dosage varies with age and body weight. APO-LEVOTHYROXINE should be given at a dose that maintains T4 or FT4 in the upper half of the normal range and serum TSH in the normal range (see 7 WARNINGS AND PRECAUTIONS, 7.1 Special Populations, 7.1.3 Pediatrics). Normalization of TSH may lag significantly behind T4 in some infants. In general, despite the smaller body size of children, the dosage (on a weight basis) required to sustain full development and general thriving is higher than in adults (see Table 1 and Table 2).
4.2 Recommended Dose and Dosage Adjustment
Recommended dosage of APO-LEVOTHYROXINE are summarized in Table 1, with additional details provided below.
Table 1 - Dosing and Administration
| Medical Condition(s) | Patient Population | Starting Dose | Dosing Increment | Interval For Monitoring/ Dosing Increment | Therapeutic Goal |
| Congenital Hypothyroidism | Neonate | 10-15 mcg/kg/day | 12.5 mcg/day† | 4-6 weeks* | FT4 level in upper half of normal range |
| Congenital/ Acquired Hypothyroidism | Infants/ Children | See Table 2 | 25 mcg/day | 1-2 months (until 1 year), 2-3 months (until 3 years), 3-12 months thereafter* | FT4 level in upper half of normal range, normal TSH |
| Congenital Hypothyroidism with risk of heart failure | Neonate | 25 mcg/day | 12.5 mcg/day† | 4-6 weeks* | T4 level in upper half of normal range, normal TSH |
| Medical Condition(s) | Patient Population | Starting Dose | Dosing Increment | Interval For Monitoring/ Dosing Increment | Therapeutic Goal |
| Severe Congenital Hypothyroidism (T4 < 5 mcg/dL) | Neonate | 50 mcg/day | 25 mcg/day | 2-4 weeks* | FT4 level in upper half of normal range, normal TSH |
| Hypothyroidism with Completed Growth and Puberty | Children | 1.6-1.7 mcg/kg/day | 25-50 mcg/day | 6-8 weeks | Normal TSH (age-specific reference range) |
| Hypothyroidism | Adults <50 years | 1.7 mcg/kg/day | 25-50 mcg/day | 6-8 weeks | Normal TSH (between 0.5 and 2.0 mU/L) |
| Adults >50 years | 25-50 mcg/day | 12.5†-25 mcg/day | 6-8 weeks | ||
| Hypothyroidism with Cardiac Disease | Adults <50 years | 25-50 mcg/day | 12.5†-25 mcg/day | 6-8 weeks | Normal TSH (between 0.5 and 2.0 mU/L) |
| Adults >50 years | 12.5†-25 mcg/day | 12.5†-25 mcg/day | 4-6 weeks | ||
| Severe Hypothyroidism | Adults < 50 years | 12.5†-25 mcg/day | 25 mcg/day | 2-4 weeks | Normal TSH (between 0.5 and 2.0 mU/L) |
| Infants/ Children | 25 mcg/day | 25 mcg/day | 2-4 weeks | Normal TSH (age-specific reference range) | |
| Hypothyroidism (short period) or Recently Treated with Hyperthyroidism | Adults > 50 years | < 1.7 mcg/kg/day | 25-50 mcg/day | 6-8 weeks | Normal TSH (between 0.5 and 2.0 mU/L) |
| Hypothyroidism with Pregnancy | Pregnant Women | 1.7 mcg/kg/day (Increased dose may be required) | 25-50 mcg/day | Every 4 weeks during first half of pregnancy; at least once between week 26 and 32; approximately 6 weeks postpartum | Normal TSH (trimester- specific) and FT4 in the upper third of normal range 1st trimester: < 2.5 mU/L 2nd trimester: < 3.0 mU/L 3rd trimester: < 3.5 mU/L |
| Secondary Hypothyroidism | Not Specified | ** | ** | ** | FT4 level in upper third of normal range |
| Tertiary Hypothyroidism | Not Specified | ** | ** | ** | FT4 level in upper third of normal range |
| Subclinical Hypothyroidism | Not Specified | 25-50 mcg/day | Adjust as necessary | 6-8 weeks | Normal TSH (between 0.5 and 2.0 mU/L) |
| Medical Condition(s) | Patient Population | Starting Dose | Dosing Increment | Interval For Monitoring/ Dosing Increment | Therapeutic Goal |
| Well-differentiated (papillary or follicular) Thyroid Cancers | Not Specified | > 2 mcg/kg/day | 25-50 mcg/day | 6-8 weeks | TSH < 0.1 mU/L TSH <0.01 mU/L for patients with high risk tumors |
† APO-LEVOTHYROXINE is not available as a 12.5 mcg dosage form. A different product should be considered. * For Congenital Hypothyroidism, the current guidelines recommend a 2 week monitoring interval at the beginning of therapy until normalization of TSH levels ** Depending on age, duration of hypothyroidism and cardiovascular risk factor FT4: free T4 TSH: Thyroid-stimulating hormone | |||||
Adult Dosage
Hypothyroidism:
The usual full replacement dose of APO-LEVOTHYROXINE for younger, healthy adults is approximately 1.7 mcg/kg/day administered once daily. Therapy is usually initiated at the anticipated full replacement dose.
In older patients, the full replacement dose may be altered by decreases in T4 metabolism and levothyroxine sodium absorption. Older patients may require less than 1 mcg/kg/day.
For most patients older than 50 years and for patients under 50 years of age with a history of/underlying cardiac disease, an initial starting dose of 25 to 50 mcg/day of levothyroxine sodium is recommended, with gradual increments in dose at six to eight week intervals, as needed. The recommended starting dose of levothyroxine sodium in patients over 50 with cardiac disease is 12.5 to 25 mcg/day, with gradual dose increments at four to six week intervals. If cardiac symptoms develop or worsen, the cardiac disease should be evaluated and the dose of levothyroxine sodium reduced. Rarely, worsening angina or other signs of cardiac ischemia may prevent achieving a TSH in the normal range.
Women who are maintained on APO-LEVOTHYROXINE during pregnancy may require increased doses (see 7 WARNINGS AND PRECAUTIONS, 7.1 Special Populations, 7.1.1 Pregnant Women).
Treatment of subclinical hypothyroidism may require lower than usual replacement doses e.g.,1.0 mcg/kg/day. Patients for whom treatment is not initiated should be monitored yearly for changes in clinical status, TSH, and thyroid antibodies.
Few patients require doses greater than 200 mcg/day. An inadequate response to daily doses of 300 to 400 mcg/day is rare, and may suggest malabsorption, poor patient compliance, and/or drug interactions.
Clinical and laboratory evaluations should be performed at 6 to 8 week intervals (2 to 3 weeks in severely hypothyroid patients), and the dosage adjusted by 12.5 to 25 mcg increments until the serum TSH concentration is normalized and signs and symptoms resolve.
Once optimal replacement is achieved, clinical and laboratory evaluations should be conducted at least annually or whenever warranted by a change in patient status.
TSH Suppression in Thyroid Cancer:
For well-differentiated thyroid cancer, TSH is generally suppressed to less than 0.1 mU/L and requires APO-LEVOTHYROXINE doses of greater than 2 mcg/kg/day.
APO-LEVOTHYROXINE should be administered with caution to patients in whom there is a suspicion of thyroid gland autonomy, in view of the fact that the effects of exogenous hormone administration will be additive to endogenous thyroid hormone production.
Pediatric Dosage
Congenital or acquired hypothyroidism:
The initial APO-LEVOTHYROXINE dose varies with age and body weight, and should be adjusted to maintain serum total T4 or FT4 levels in the upper half of the normal range. The recommended dose per body weight decreases with age. In general, unless there are overriding clinical concerns, therapy in children is usually initiated at the full replacement dose (see Table 2). Infants and neonates with very low (< 5 mcg/dL) or undetectable serum T4 levels should be started at higher end of the dosage range (e.g., 50 mcg daily). A lower dose (e.g., 25 mcg daily) should be considered for neonates at risk of cardiac failure, increasing every few days until a full maintenance dose is reached. Children with underlying heart disease should be started at lower dosages, with careful upward titration. In children with severe, longstanding hypothyroidism or pre-existing cardiac insufficiency, APO-LEVOTHYROXINE should be initiated gradually, with an initial 25 mcg dose for two weeks, then increasing by 25 mcg every 2 to 4 weeks until the desired dose, based on serum T4 and TSH levels, is achieved. (see 7 WARNINGS AND PRECAUTIONS, 7.1 Special Populations, 7.1.3 Pediatrics).
Table 2 - Dosage Guidelines for Pediatric Hypothyroidism
| Age | Daily dose (mcg) per kg of body weight * |
| 0 - 3 months | 10 – 15 mcg/kg/day |
| 3 - 6 months | 8 – 10 mcg/kg/day |
| 6 - 12 months | 6 – 8 mcg/kg/day |
| 1 - 5 years | 5 – 6 mcg/kg/day |
| 6 - 12 years | 4 – 5 mcg/kg/day |
| > 12 years but growth and puberty incomplete | 2 – 3 mcg/kg/day |
| Growth and puberty complete | 1.6 – 1.7 mcg/kg/day |
| *To be adjusted on the basis of clinical response and laboratory tests (see 7 WARNINGS AND PRECAUTIONS, 7.1 Special Populations, 7.1.3 Pediatrics). | |
Serum T4 and TSH measurements should be evaluated at the following intervals, with subsequent dosage adjustments to normalize serum total T4 or FT4 and TSH:
- 2 and 4 weeks after therapy initiation, until complete normalization of TSH,
- every 1 to 2 months during the first year of life,
- every 2 to 3 months between 1 and 3 years of age,
- every 3 to 12 months thereafter until growth is completed
Evaluation at more frequent intervals is indicated when compliance is questioned or abnormal laboratory values are obtained. Patient evaluation is also advisable approximately 2 to 4 weeks after any change in APO-LEVOTHYROXINE dose.
4.4 Administration
Adults
Administer APO-LEVOTHYROXINE as a single daily dose, preferably on an empty stomach, one-half to one-hour before breakfast. As food and drink can significantly change the absorption of levothyroxine sodium, patients should be advised to take levothyroxine sodium at the same time every day and be consistent in how they take it with regards to meals.
Administer APO-LEVOTHYROXINE at least 4 hours before or after drugs that are known to interfere with its absorption (see 9 DRUG INTERACTIONS).
Evaluate the need for dose adjustments when regularly administering within one hour of certain foods that may affect APO-LEVOTHYROXINE absorption (see 9 DRUG INTERACTIONS and 10 CLINICAL PHARMACOLOGY).
Pediatrics
APO-LEVOTHYROXINE tablets may be given to infants and children who cannot swallow intact tablets by crushing the tablet and suspending the freshly crushed tablet in a small amount of water (5 to 10 mL), breast milk or non-soybean based formula. The suspension can be given by spoon or dropper. DO NOT STORE THE SUSPENSION FOR ANY PERIOD OF TIME. The crushed tablet may also be sprinkled over a small amount of food, such as apple sauce. Foods or formula containing large amounts of soybean, fibre, or iron should not be used for administering APO-LEVOTHYROXINE.
4.5 Missed Dose
If a scheduled dose is missed, the dose should be taken as soon as the patient remembers it. However, if it is almost time for the next dose, the missed dose can be skipped and the regular dosing schedule continued. Two doses should not be taken together. If more than two doses are missed, the patient should contact their healthcare professional.
5 OVERDOSAGE
Signs and Symptoms
Excessive doses of levothyroxine sodium result in a hypermetabolic state indistinguishable from thyrotoxicosis of endogenous origin. Signs and symptoms of thyrotoxicosis include exophthalmic goiter, weight loss, increased appetite, palpitations, nervousness, diarrhea, abdominal cramps, sweating, tachycardia, increased pulse and blood pressure, cardiac arrhythmias, angina pectoris, tremors, insomnia, heat intolerance, fever, and menstrual irregularities. In addition, confusion and disorientation may occur. Cerebral embolism, shock, coma, and death have been reported. Seizures have occurred in a child ingesting 18 mg of levothyroxine. Overdose of APO-LEVOTHYROXINE may result in hyperthyroidism and could lead to symptoms of acute psychosis, especially in patients at risk of psychotic disorders. Symptoms are not always evident or may not appear until several days after ingestion of APO-
LEVOTHYROXINE.
Treatment of Overdosage
APO-LEVOTHYROXINE should be reduced in dose or temporarily discontinued if signs and symptoms of overdosage appear.
In the treatment of acute massive APO-LEVOTHYROXINE overdosage, symptomatic and supportive therapy should be instituted immediately. Treatment is aimed at reducing gastrointestinal absorption and counteracting central and peripheral effects, mainly those of increased sympathetic activity. The stomach should be emptied immediately by emesis or gastric lavage if not otherwise contraindicated (e.g., by coma, convulsions or loss of gag reflex). Cholestyramine and activated charcoal have also been used to decrease levothyroxine sodium absorption. Beta-receptor antagonists, particularly propranolol, are useful in counteracting many of the effects of increased central and peripheral sympathetic activity, especially when no contraindications exist for its use. Provide respiratory support as needed; control congestive heart failure and arrhythmia, control fever, hypoglycemia, and fluid loss as necessary. Large doses of antithyroid drugs (e.g., methimazole, carbimazole, or propylthiouracil) followed in one to two hours by large doses of iodine may be given to inhibit synthesis and release of thyroid hormones. Cardiac glycosides may be administered if congestive heart failure develops. Glucocorticoids may be administered to inhibit the conversion of T4 to T3. Plasmapheresis, charcoal hemoperfusion and exchange transfusion have been reserved for cases in which continued clinical deterioration occurs despite conventional therapy. Since T4 is extensively protein bound, very little drug will be removed by dialysis.
| For management of a suspected drug overdose, contact your regional poison control centre. |
|---|
6 DOSAGE FORMS, STRENGTHS, COMPOSITION AND PACKAGING
Table 3 - Dosage Forms, Strengths, Composition and Packaging
| Route of Administration | Dosage Form / Strength/Composition | Non-medicinal Ingredients |
|---|---|---|
| oral | Tablet, 25 mcg, 50 mcg, 75 mcg, 88 mcg, 100 mcg, 112 mcg, 125 mcg, 137 mcg, 150 mcg, 175 mcg, 200 mcg and 300 mcg of levothyroxine sodium. | Aluminium hydroxide (25, 75, 88, 100, 112, 125, 137, 150, 175, 200, 300 mcg), croscarmellose sodium, D & C Yellow No. 10 (300 mcg), FD & C Blue No. 1 (88, 125, 137, 300 mcg), FD & C Blue No. 2 (75, 150, 175 mcg), FD & C Red No.40 (75, 112, 125, 175, 200 mcg), FD & C Yellow No.6 (25, 88, 100, 125, 300 mcg), microcrystalline cellulose, silicon dioxide, sodium chloride (25, 75, 88, 100, 112, 125, 137, 150, 175, 200, 300 mcg), sodium sulphate (25, 75, 88, 100, 112, 125, 137, 150, 175, 200, 300 mcg), and sodium stearyl fumarate. |
* colour additives by tablet strength are shown in Table 4.
†The 50 mcg tablet is formulated without colour additives for patients who are sensitive to dyes.
APO-LEVOTHYROXINE (levothyroxine tablets):
| 25 mcg: | Orange coloured, circular tablets debossed with ‘M56’ on one side and break line on the other side. |
| 50 mcg: | White to off-white coloured, circular tablets, debossed with ‘M57’ on one side and break line on the other side. |
| 75 mcg: | Violet coloured, circular tablets, debossed with 'M58' on one side and break line on the other side. |
| 88 mcg: | Olive coloured, circular tablets, debossed with 'M59' on one side and break line on the other side. |
| 100 mcg: | Yellow coloured, circular tablets, debossed with 'M60' on one side and break line on the other side. |
| 112 mcg: | Rose coloured, circular tablets, debossed with 'M61' on one side and break line on the other side. |
| 125 mcg: | Brown coloured, circular tablets, debossed with 'M62' on one side and break line on the other side. |
| 137 mcg: | Turquoise coloured, circular tablets, debossed with 'M63' on one side and break line on the other side. |
| 150 mcg: | Blue coloured, circular tablets, debossed with 'M64' on one side and break line on the other side. |
| 175 mcg: | Lilac coloured, circular tablets, debossed with 'M65' on one side and break line on the other side. |
| 200 mcg: | Pink coloured, circular tablets, debossed with 'M66' on one side and break line on the other side. |
| 300 mcg: | Green coloured, circular tablets, debossed with 'M67' on one side and break line on the other side. |
The strengths available, including colour additives by tablet strength, and packaging sizes are as follows (see Table 4):
Table 4. APO-LEVOTHYROXINE Tablet Characteristics
| Strength (mcg) | Tablet Colour | Colour Additive(s) | Pack Size |
| 25 | Orange | FD&C Yellow No. 6 Al lake | Available in bottles of 100 and 1000 tablets |
| 50 | White to off-white | None | Available in bottles of 100 and 1000 tablets |
| 75 | Violet | FD&C Red No. 40 Al lake FD&C Blue No. 2 Al lake | Available in bottles of 100 and 1000 tablets |
| 88 | Olive | FD&C Blue No. 1 Al lake FD&C Yellow No. 6 Al lake | Available in bottles of 100 and 1000 tablets |
| Strength (mcg) | Tablet Colour | Colour Additive(s) | Pack Size |
| 100 | Yellow | FD&C Yellow No. 6 Al lake | Available in bottles of 100 and 1000 tablets |
| 112 | Rose | FD&C Red No. 40 Al lake | Available in bottles of 100 and 1000 tablets |
| 125 | Brown | FD&C Yellow No. 6 Al lake FD&C Red No. 40 Al lake FD&C Blue No. 1 Al lake | Available in bottles of 100 and 1000 tablets |
| 137 | Turquoise | FD&C Blue No. 1 Al lake | Available in bottles of 100 and 1000 tablets |
| 150 | Blue | FD&C Blue No. 2 Al lake | Available in bottles of 100 and 1000 tablets |
| 175 | Lilac | FD&C Blue No. 2 Al lake FD&C Red. No. 40 Al lake | Available in bottles of 100 and 1000 tablets |
| 200 | Pink | FD&C Red No. 40 Al lake | Available in bottles of 100 and 1000 tablets |
| 300 | Green | D&C Yellow No. 10 lake, FD&C Yellow No. 6 Al lake and FD&C Blue No. 1 Al lake | Available in bottles of 100 tablets |
7 WARNINGS AND PRECAUTIONS
Please see 3 SERIOUS WARNINGS AND PRECAUTIONS BOX.
General
APO-LEVOTHYROXINE has a narrow therapeutic index. Regardless of the indication for use, careful dosage titration is necessary to avoid the consequences of over- or under- treatment. These consequences include, among others, effects on growth and development, cardiovascular function, bone metabolism, reproductive function, cognitive function, emotional state, gastrointestinal function, and on glucose and lipid metabolism. Many drugs interact with APO-LEVOTHYROXINE necessitating adjustments in dosing or monitoring of clinical or laboratory parameters to maintain therapeutic response (see 9 DRUG INTERACTIONS).
The bioavailability of levothyroxine may differ to some extent among marketed brands. Once the patient is stabilized on a particular brand of levothyroxine sodium, caution should be exercised when a change in drug product brand is implemented. Unless bioequivalence has been established (see 14.3 Comparative Bioavailability Studies), if a switch to another levothyroxine-containing product is required, there is a need to undertake close clinical and biological monitoring during the transition period due to a potential risk of imbalance. In some patients, a dose adjustment could be necessary.
It has been shown that differences in formulations of levothyroxine, despite an identical content of active ingredient, may be associated with differences in fractional gastrointestinal absorption. These differences may not be observed through measurement of total T3 and T4 serum levels. Therefore, unless bioequivalence has been established (see 14.3 Comparative Bioavailability
Studies), it is recommended that patients who are switched from one levothyroxine formulation to another be re-titrated to the desired thyroid function. Accuracy in re-titration can best be achieved by using sensitive thyrotropin assays.
Seizures have been reported rarely in association with the initiation of levothyroxine sodium therapy, and may be related to the effect of thyroid hormone on seizure threshold.
Carcinogenesis and Mutagenesis
Although animal studies to determine the mutagenic or carcinogenic potential of thyroid hormones have not been performed, synthetic T4 is identical to that produced by the human thyroid gland. A reported association between prolonged thyroid hormone therapy and breast cancer has not been confirmed and patients receiving levothyroxine sodium for established indications should not discontinue therapy.
Cardiovascular
APO-LEVOTHYROXINE should be used with caution in patients with cardiovascular disorders, including angina, coronary artery disease, and hypertension, and in the elderly who have a greater likelihood of occult cardiac disease. In these patients, levothyroxine sodium therapy should be initiated at lower doses than those recommended in younger individuals or in patients without cardiac diseases (see 7 WARNINGS AND PRECAUTIONS, 7.1 Special Populations, 7.1.4 Geriatrics and 4 DOSAGE AND ADMINISTRATION). If cardiac symptoms develop or worsen, the levothyroxine sodium dose should be reduced or withheld for one week and then cautiously restarted at a lower dose. Over-treatment with APO-LEVOTHYROXINE may have adverse cardiovascular effects such as an increase in heart rate, cardiac wall thickness, and cardiac contractility and may precipitate angina or arrhythmias.
Patients with coronary artery disease who are receiving levothyroxine sodium therapy should be monitored closely during surgical procedures, since the possibility of precipitating cardiac arrhythmias may be greater in those treated with levothyroxine. Concomitant administration of thyroid hormone and sympathomimetic agents to patients with coronary artery disease may increase the risk of coronary insufficiency.
Driving and Operating Machinery
Exercise caution when driving or operating a vehicle or potentially dangerous machinery.
Endocrine and Metabolism
Thyroid hormones, either alone or together with other therapeutic agents, should not be used for the treatment of obesity or for weight loss. In euthyroid patients, doses within the range of daily hormonal requirements are ineffective for weight reduction. Larger doses may produce serious or even life-threatening manifestations of toxicity, particularly when given in association with sympathomimetic amines such as those used for their anorectic effects.
Patients treated concomitantly with APO-LEVOTHYROXINE and orlistat should be monitored for changes in thyroid function (see 9 DRUG INTERACTIONS). Hypothyroidism and/or reduced control of hypothyroidism may occur. The mechanism may involve a decreased absorption of iodine salts and/or levothyroxine.
Effects on Bone Mineral Density
In women, long-term levothyroxine therapy has been associated with increased bone resorption, thereby decreasing bone mineral density, especially in postmenopausal women on greater replacement doses or in women who are receiving suppressive doses of levothyroxine sodium. The increased bone resorption may be associated with increased serum levels and urinary excretion of calcium and phosphorous, elevations in bone alkaline phosphatase and suppressed serum parathyroid hormone levels. Therefore, it is recommended that patients receiving APO-LEVOTHYROXINE be given the minimum dose necessary to achieve the desired clinical and biochemical response.
Patients with Nontoxic Diffuse Goiter or Nodular Thyroid Disease
In patients with non-toxic diffuse goiter or nodular thyroid disease, particularly the elderly or those with underlying cardiovascular disease, levothyroxine therapy is contraindicated if the serum TSH level is already suppressed due to the risk of precipitating overt thyrotoxicosis (see 2 CONTRAINDICATIONS).
Hypothalamic/pituitary Hormone Deficiencies
In patients with secondary or tertiary hypothyroidism, additional hypothalamic/pituitary hormone deficiencies should be considered, and, if diagnosed, treated by adequate adrenal replacement therapy before starting the therapy with levothyroxine, to prevent acute adrenal insufficiency (see 2 CONTRAINDICATIONS).
Myxedema Coma
Myxedema coma represents the extreme expression of severe hypothyroidism and is considered a medical emergency. It is a life-threatening emergency characterized by poor circulation and hypometabolism, and may result in unpredictable absorption of levothyroxine sodium from the gastrointestinal tract. Therefore, oral thyroid hormone drug products, such as APO-LEVOTHYROXINE, are not recommended to treat this condition. Thyroid hormone products formulated for intravenous administration should be administered.
Gastrointestinal
Thyroxine absorption is decreased in patients with malabsorption syndromes. It is advised to treat the malabsorption condition to ensure effective thyroxine treatment with regular thyroxine dose.
Hematologic
T4 enhances the response to anticoagulant therapy. Prothrombin time should be closely monitored in patients taking both APO-LEVOTHYROXINE and oral anticoagulants, and the dosage of anticoagulant adjusted accordingly.
Immune
Autoimmune Polyglandular Syndrome
Occasionally, chronic autoimmune thyroiditis may occur in association with other autoimmune disorders such as adrenal insufficiency, pernicious anemia, and insulin-dependent diabetes mellitus. Use of APO-LEVOTHYROXINE in patients with concomitant diabetes mellitus, diabetes insipidus or adrenal cortical insufficiency may aggravate the intensity of their symptoms.
Appropriate adjustments of the various therapeutic measures directed at these concomitant endocrine diseases may therefore be required. Treatment of myxedema coma may require simultaneous administration of glucocorticoids (see 4 DOSAGE AND ADMINISTRATION).
Monitoring and Laboratory Tests
Treatment of patients with APO-LEVOTHYROXINE requires periodic assessment of thyroid status by appropriate laboratory tests and clinical evaluation. Selection of appropriate tests for the diagnosis and management of thyroid disorders depends on patient variables such as presenting signs and symptoms, pregnancy, and concomitant medications. Measurement of FT4 and TSH levels, using a sensitive TSH assay, is recommended to confirm a diagnosis of thyroid disease. Normal ranges for these parameters are age-specific in newborns and younger children.
TSH alone or initially may be useful for thyroid disease screening and for monitoring therapy for primary hypothyroidism as a linear inverse correlation exists between serum TSH and FT4. Measurement of total serum T4 and T3, resin T3 uptake, and free T3 concentrations may also be useful. Antithyroid microsomal antibodies are an indicator of autoimmune thyroid disease.
Positive microsomal antibody presence in an euthyroid patient is a major risk factor for the development of hypothyroidism. An elevated serum TSH in the presence of a normal T4 may indicate subclinical hypothyroidism. Intracellular resistance to thyroid hormone is quite rare, and is suggested by clinical signs and symptoms of hypothyroidism in the presence of high serum T4 levels.
Adequacy of levothyroxine sodium therapy for hypothyroidism of pituitary or hypothalamic origin should be assessed by measuring FT4, which should be maintained in the upper half of the normal range. Measurement of TSH is not a reliable indicator of response to therapy for this condition.
Adequacy of levothyroxine sodium therapy for congenital and acquired pediatric hypothyroidism should be assessed by measuring serum total T4 or FT4; these should be maintained in the upper half of the normal range. In congenital hypothyroidism, serum TSH normalization may lag behind serum T4 normalization by 2 to 3 months or longer. Rarely, in some patients, serum TSH remains relatively elevated despite clinical euthyroidism and age-specific normal T4 or FT4 levels (see 7 WARNINGS AND PRECAUTIONS, 7.1 Special Populations, 7.1.3 Pediatrics).
Serum biotin may interfere with thyroid function immunoassays that are based on a biotin/streptavidin interaction, leading to either falsely decreased or falsely increased test results (see 9.7 Drug-Laboratory Test Interaction). The risk of interference increases with higher doses of biotin. When possible, it is recommended that patients abstain from taking biotin supplements for at least 2 days prior to specimen collection.
When interpreting results of laboratory tests, possible biotin interference has to be taken into consideration, especially if a lack of coherence with the clinical presentation is observed.
Psychiatric
When initiating APO-LEVOTHYROXINE therapy in patients at risk of psychotic disorders, it is recommended to start at a low APO-LEVOTHYROXINE dose at the beginning of the therapy, and to slowly increase the dosage thereafter. Monitoring of the patient is advised. If signs of psychotic disorders occur, adjustment of the dose of levothyroxine should be considered.
Reproductive Health: Female and Male Potential
Fertility
The use of levothyroxine sodium is unjustified in the treatment of male or female infertility unless this condition is associated with hypothyroidism.
7.1 Special Populations
7.1.1 Pregnant Women
Studies in pregnant women have not shown that levothyroxine sodium increases the risk of fetal abnormalities if administered during pregnancy. If levothyroxine sodium is used during pregnancy, the possibility of fetal harm appears remote.
Thyroid hormones cross the placental barrier to some extent. T4 levels in the cord blood of athyroid fetuses have been shown to be about one-third of maternal levels. Nevertheless, maternal-fetal transfer of T4 may not prevent in utero hypothyroidism.
Hypothyroidism during pregnancy is associated with a higher rate of complications, including spontaneous abortion, preeclampsia, stillbirth and premature delivery. Maternal hypothyroidism may have an adverse effect on fetal and childhood growth and development. On the basis of current knowledge, APO-LEVOTHYROXINE should not be discontinued during pregnancy, and hypothyroidism diagnosed during pregnancy should be treated. Studies have shown that during pregnancy T4 concentrations may decrease and TSH concentrations may increase to values outside normal ranges. As such, trimester-specific TSH reference values are recommended (see 4 DOSAGE & ADMINISTRATION, 4.2 Recommended Dose and Dosage Adjustment, Table 1). Postpartum values are similar to preconception values. Elevations in TSH may occur as early as the fourth week of gestation.
Combination therapy of hyperthyroidism with levothyroxine and anti-thyroid agents is contraindicated in pregnancy. Such combination would require higher doses of anti-thyroid agents such as methimazole and propylthiouracil, which are known to pass the placenta and to induce hypothyroidism in the infant.
Pregnant women who are maintained on APO-LEVOTHYROXINE should have their TSH measured approximately every 4 weeks during the first half of pregnancy, and at least once between week 26 and 32, as levothyroxine dose adjustments are often required.
An elevated TSH should be corrected by an increase in levothyroxine sodium dose. After pregnancy, the dose can be decreased to the optimal preconception dose. A serum TSH level should be obtained approximately six weeks postpartum.
7.1.2 Breast-feeding
Minimal amounts of thyroid hormones are excreted in human milk. While caution should be exercised when APO-LEVOTHYROXINE is administered to a breast-feeding woman, adequate replacement doses of levothyroxine sodium are generally needed to maintain normal lactation.
7.1.3 Pediatrics
Pediatrics (All ages including neonates): Haemodynamic parameters should be monitored when levothyroxine therapy is initiated in very low birth weight preterm neonates as circulatory collapse may occur due to the immature adrenal function.
Congenital hypothyroidism
Infants with congenital hypothyroidism appear to be at increased risk for other congenital anomalies, with cardiovascular anomalies (pulmonary stenosis, atrial septal defect, and ventricular septal defect) being the most common association.
Rapid restoration of normal serum T4 concentrations is essential to prevent deleterious neonatal thyroid hormone deficiency effects on intelligence, overall growth, and development. Treatment should be initiated immediately upon diagnosis and generally maintained for life. The therapeutic goal is to maintain serum total T4 or FT4 in the upper half of the normal range and serum TSH in the normal range.
Prolonged use of large doses in infants may be associated with temperament problems, which appear to be transient.
Thyroid function tests (serum total T4 or FT4, and TSH) should be monitored closely and used to determine the adequacy of levothyroxine sodium therapy. Serum T4 normalization is usually followed by a rapid decline in TSH. Nevertheless, TSH normalization may lag behind T4 normalization by 2 to 3 months or longer. The relative serum TSH elevation is more marked in the early months, but can persist to some degree throughout life. In rare patients TSH remains relatively elevated despite clinical euthyroidism and age-specific normal total T4 or FT4 levels. Increasing the levothyroxine sodium dosage to suppress TSH into the normal range may produce overtreatment, with an elevated serum T4 and clinical features of hyperthyroidism including: irritability, increased appetite with diarrhea, and sleeplessness. Another risk of prolonged overtreatment in infants is premature cranial synostosis.
Acquired hypothyroidism
Treated children may resume growth at a greater than normal rate (period of transient catch-up growth). In some cases, the catch-up may be adequate to normalize growth. However, severe and prolonged hypothyroidism may reduce adult height. Excessive thyroxine replacement may initiate accelerated bone maturation, producing disproportionate skeletal age advancement and shortened adult stature.
If transient hypothyroidism is suspected hypothyroidism permanence may be assessed after the child reaches 3 years of age. Levothyroxine therapy may be interrupted for 30 days and serum T4 and TSH measured. Low T4 and elevated TSH confirm permanent hypothyroidism; therapy should be re-instituted. If T4 and TSH remain in the normal range, a presumptive diagnosis of transient hypothyroidism can be made. In this instance, continued clinical monitoring and periodic thyroid function test re-evaluation may be warranted.
Since some more severely affected children may become clinically hypothyroid when treatment is discontinued for 30 days, an alternate approach is to reduce the replacement dose of APO-LEVOTHYROXINE by half during the 30-day trial period. If, after 30 days, the serum TSH is elevated above 20 mU/L, the diagnosis of permanent hypothyroidism is confirmed, and full replacement therapy should be resumed. However, if the serum TSH has not risen to greater than 20 mU/L, APO-LEVOTHYROXINE treatment should be discontinued for another 30-day trial period followed by repeat serum T4 and TSH testing.
7.1.4 Geriatrics
Because of the increased prevalence of cardiovascular disease among the elderly, levothyroxine therapy should not be initiated at the full replacement dose (see 7 WARNINGS AND PRECAUTIONS, Cardiovascular and 4 DOSAGE AND ADMINISTRATION, 4.2 Recommended Dose and Dosage Adjustment). Atrial arrhythmias can occur in elderly patients. Atrial fibrillation is the most common of the arrhythmias observed with levothyroxine overtreatment in the elderly.
8 ADVERSE REACTIONS
8.1 Adverse Reaction Overview
Inadequate doses of APO-LEVOTHYROXINE may produce or fail to resolve symptoms of hypothyroidism.
Adverse reactions associated with levothyroxine sodium are primarily those of thyrotoxicosis due to therapeutic overdosage (see 7 WARNINGS AND PRECAUTIONS and 5 OVERDOSAGE).
Adverse reactions observed with levothyroxine use include the following:
| Cardiac disorders: | palpitations, tachycardia, arrhythmias, increased pulse and blood pressure, cardiac failure, angina, myocardial infarction and cardiac arrest |
|---|---|
| Gastrointestinal System: | diarrhea, vomiting and abdominal cramps |
| General: | fatigue, heat intolerance, fever and excessive sweating |
| Immune system disorders: | Hypersensitivity reactions to inactive ingredients have occurred in patients treated with thyroid hormone products. These include urticaria, pruritus, skin rash, flushing, angioedema, various GI symptoms (abdominal pain, nausea, vomiting and diarrhea), fever, arthralgia, serum sickness and wheezing. Hypersensitivity to levothyroxine itself is not known to occur. |
| Investigations: | decreased bone mineral density, elevations in liver function tests |
| Metabolism and nutrition disorders: | increased appetite, weight loss |
| Musculoskeletal and connective tissue: | tremors, muscle weakness, slipped capital femoral epiphysis in children, excessive dose may result in craniosynostosis and premature closure of the epiphyses in children (with resultant compromised adult height) |
| Nervous System: | headache, pseudotumor cerebri, seizures |
| Psychiatric disorders: | hyperactivity, nervousness, anxiety, irritability, emotional lability and insomnia |
| Reproductive System: | menstrual irregularities, impaired fertility |
| Respiratory System: | dyspnea |
|---|---|
| Skin and subcutaneous tissue disorders: | alopecia (generally transient) |
| Vascular disorders: | flushing |
9 DRUG INTERACTIONS
9.2 Drug Interactions Overview
The magnitude and relative clinical importance of the effects noted below are likely to be patient-specific and may vary by such factors as age, gender, race, intercurrent illnesses, dose of either agent, additional concomitant medications, and timing of drug administration. Any agent that alters thyroid hormone synthesis, secretion, distribution, effect on target tissues, metabolism, or elimination may alter the optimal therapeutic dose of APO-LEVOTHYROXINE.
9.3 Drug-Behavioural Interactions
This information is not available for this drug product.
9.4 Drug-Drug Interactions
Many drugs affect thyroid hormone pharmacokinetics and metabolism (e.g., absorption, synthesis, secretion, catabolism, protein binding, and target tissue response) and may alter the therapeutic response to APO-LEVOTHYROXINE. In addition, thyroid hormones and thyroid status have varied effects on the pharmacokinetics and actions of other drugs. A listing of drug-thyroidal axis interactions is contained in Table 5.
The list of drug-thyroidal axis interactions in Table 5 may not be comprehensive due to the introduction of new drugs that interact with the thyroidal axis or the discovery or previously unknown interactions. The prescriber should be aware of this fact and should consult appropriate reference sources (e.g., package inserts of newly approved drugs, medical literature) for additional information if a drug-drug interaction with levothyroxine is suspected.
The drugs listed in this table are based on either drug interaction case reports or studies, or potential interactions due to the expected magnitude and seriousness of the interaction (i.e., those identified as contraindicated).
Table 5 - Established or Potential Drug-Drug Interactions (Drug-Thyroidal Axis Interactions)
| Proper/Common name | Effect |
| Drugs that may reduce TSH secretion - the reduction is not sustained; therefore, hypothyroidism does not occur | |
Dopamine/Dopamine Agonists Glucocorticoids Octreotide | Use of these agents may result in a transient reduction in TSH secretion when administered at the following doses:
|
| Proper/Common name | Effect |
| |
| Drugs that alter thyroid hormone secretion | |
| Drugs that may decrease thyroid hormone secretion, which may result in hypothyroidism | |
Aminoglutethimide Amiodarone Iodide (including iodine-containing radiographic contrast agents) Lithium Thioamides
Sulfonamides Tolbutamide | Long-term aminoglutethimide therapy may minimally decrease T4 and T3 levels and increase TSH, although all values remain within normal limits in most patients. Oral cholecystographic agents and amiodarone are slowly excreted, producing more prolonged hypothyroidism than parenterally administered iodinated contrast agents. The fetus, neonate, elderly and euthyroid patients with underlying thyroid disease (e.g., Hashimotos’s thyroiditis or with Grave’s disease previously treated with radioiodine or surgery) are among those individuals who are particularly susceptible to iodine-induced hypothyroidism. Long-term lithium therapy can result in goiter in up to 50% of patients, and either subclinical or overt hypothyroidism, each in up to 20% of patients. Lithium blocks the TSH-mediated release of T4 and T3. Thyroid function should therefore be carefully monitored during lithium initiation, stabilization, and maintenance. If hypothyroidism occurs during lithium treatment, a higher than usual APO-LEVOTHYROXINE dose may be required. |
| Drugs that may increase thyroid hormone secretion, which may result in hyperthyroidism | |
Amiodarone Iodide (including iodine-containing radiographic contrast agents) | Iodide and drugs that contain pharmacologic amounts of iodide may cause hyperthyroidism in euthyroid patients with Grave’s disease previously treated with antithyroid drugs or in euthyroid patients with thyroid autonomy (e.g., multinodular goiter or hyperfunctioning thyroid adenoma). Hyperthyroidism may develop over several weeks and may persist for several months after therapy discontinuation. Amiodarone may induce hyperthyroidism by causing thyroiditis. |
| Proper/Common name | Effect |
| Drugs that may decrease T4 absorption, which may result in hypothyroidism | |
Anion/ Cation Exchange Resins -Sevelamer -Sodium Polystyrene Sulfonate Antacids
-Simethicone Bile Acid Sequestrants
Calcium Carbonate Ferrous Sulfate Lanthanum carbonate Orlistat Sucralfate | Concurrent use may reduce the efficacy of levothyroxine by binding and delaying or preventing absorption, potentially resulting in hypothyroidism. Calcium carbonate may form an insoluble chelate with levothyroxine, and ferrous sulfate likely forms a ferric-thyroxine complex. Administer levothyroxine at least four (4) hours apart from these agents. Patients treated concomitantly with orlistat and levothyroxine should be monitored for changes in thyroid function. Hypothyroidism and/or reduced control of hypothyroidism may occur. The mechanism, although not proven, may involve a decreased absorption of iodine salts and/or levothyroxine. |
| Drugs that may alter T4 and T3 serum transport - but FT4 concentration remains normal; and therefore, the patient remains euthyroid | |
Clofibrate Estrogen-containing Oral Contraceptives Estrogens (oral) Heroin/Methadone 5-Fluorouracil Mitotane Tamoxifen | Increase serum thyroxin-binding globulin (TBG) Concentration |
Androgens/Anabolic Steroids Asparaginase Glucocorticoids Slow-Release Nicotinic Acid | Decrease serum TBG Concentration |
| Drugs that may cause protein-binding site replacement | |
Furosemide (greater than 80 mg IV) Heparin Hydantoins Non Steroidal Anti-Inflammatory Drugs
| Administration of these agents with levothyroxine results in an initial transient increase in FT4. Continued administration results in a decrease in Serum T4 and normal FT4 and TSH concentrations and, therefore, patients are clinically euthyroid. Salicylates inhibit binding of T4 and T3 to TBG and transthyretin. An initial increase in serum FT4 is followed by return of FT4 to normal levels with sustained therapeutic serum saliyclate concentrations, although total T4 levels may decrease by as much as 30%. |
| Drugs that may alter T4 and T3 metabolism | |
| Drugs that may increase hepatic metabolism, which may result in hypothyroidism | |
| Proper/Common name | Effect |
Carbamazepine Hydantoins Phenobarbital Rifampin Ritonavir | Stimulation of hepatic microsomal drug-metabolizing enzyme activity may cause increased hepatic degradation of levothyroxine, resulting in increased levothyroxine requirements. Phenytoin and carbamazepine reduce serum protein binding of levothyroxine, and total and FT4 may be reduced by 20 to 40%, but most patients have normal serum TSH levels and are clinically euthyroid. Post marketing cases have been reported indicating a potential interaction between ritonavir containing products and levothyroxine, resulting in TSH increased levels and hypothyroidism. TSH should be monitored in patients treated concomitantly with ritonavir and levothyroxine for at least the first month after starting and/or ending ritonavir treatment, and levothyroxine dose should be adjusted as needed. |
| Drugs that may decrease T4 5'-deiodinase activity | |
Amiodarone Beta-adrenergic antagonists (e.g., propanolol greater than 160 mg/day) Glucocorticoids (e.g., dexamethasone greater than or equal to 4 mg/day) Propylthiouracil (PTU) | Administration of these enzyme inhibitors decreases the peripheral conversion of T4 to T3, leading to decreased T3 levels. However, serum T4 levels are usually normal but may occasionally be slightly increased. In patients treated with large doses of propanolol (greater than 160 mg/day), T3 and T4 levels change slightly, TSH levels remain normal, and patients are clinically euthyroid. It should be noted that actions of particular beta-adrenergic antagonists may be impaired when the hypothyroid patient is converted to the euthyroid state. Short-term administration of large doses of glucocorticoids may decrease serum T3 concentrations by 30% with minimal change in serum T4 levels. However, long-term glucocorticoid therapy may result in slightly decreased T3 and T4 levels due to decreased TBG production (see above). |
| Miscellaneous | |
Anticoagulants (oral)
| Thyroid hormones appear to increase the catabolism of vitamin K- dependent clotting factors, thereby increasing the anticoagulant activity of oral anticoagulants. Therefore, a decrease in the dose of anticoagulant may be warranted with correction of the hypothyroid state or when the levothyroxine sodium dose is increased. Prothrombin time should be carefully monitored in patients taking levothyroxine and oral anticoagulants and the dose of anticoagulant therapy adjusted accordingly. |
| Proper/Common name | Effect |
Antidepressants
| Concurrent use of tri/tetracyclic antidepressants and levothyroxine may increase the therapeutic and toxic effects of both drugs, possibly due to increased receptor sensitivity to catecholamines. Toxic effects may include increased risk of cardiac arrhythmias and CNS stimulation; onset of action of tricyclics may be accelerated. Administration of sertraline in patients stabilized on levothyroxine may result in increased levothyroxine requirements. |
Antidiabetic Agents
| Addition of levothyroxine to antidiabetic or insulin therapy may result in increased antidiabetic agent or insulin requirements. Careful monitoring of diabetic control is recommended, especially when thyroid therapy is started, changed, or discontinued. |
| Cardiac glycosides | Serum digitalis glycoside levels may be reduced in hyperthyroidism or when the hypothyroid patient is converted to the euthyroid state, necessitating an increase in the dose of digitalis glycosides. Therapeutic effect of digitalis glycosides may be reduced by levothyroxine sodium. |
Cytokines
| Therapy with interferon-alpha has been associated with the development of antithyroid microsomal antibodies in 20% of patients and some have transient hypothyroidism, hyperthyroidism, or both. Patients who have antithyroid antibodies before treatment are at higher risk for thyroid dysfunction during treatment. Interleukin-2 has been associated with transient painless thyroiditis in 20% of patients. Interferon-beta and -gamma have not been reported to cause thyroid dysfunction. |
Growth Hormones
| Excessive use of thyroid hormones with growth hormones may accelerate epiphyseal closure. However, untreated hypothyroidism may interfere with growth response to growth hormone. |
| Ketamine | Concurrent use may produce marked hypertension and tachycardia; cautious administration to patients receiving thyroid hormone therapy is recommended. |
| Methylxanthine Bronchodilators (e.g., theophylline) | Decreased theophylline clearance may occur in hypothyroid patients; clearance returns to normal when the euthyroid state is achieved. |
| Radiographic agents | Thyroid hormones may reduce the uptake of 123I, 131I, and 99mTc. |
| Sympathomimetics | Concurrent use may increase the effects of sympathomimetics or thyroid hormone. Thyroid hormones may increase the risk of coronary insufficiency when sympathomimetic agents are administered to patients with coronary artery disease. |
| Proper/Common name | Effect |
| Tyrosine Kinase Inhibitors | Plasma concentration of levothyroxine (thyroxine) possibly reduced by Tyrosine Kinase Inhibitors (e.g. imatinib, sunitinib). |
| Proton Pump Inhibitors | Plasma concentration of levothyroxine (thyroxine) possibly reduced by Proton Pump Inhibitors. Monitoring of TSH plasma level is recommended. |
Chloral Hydrate Ciprofloxacin Diazepam Ethionamide Lovastatin Metoclopramide 6-Mercaptopurine Nitroprusside Para-aminosalicylate sodium Perphenazine Resorcinol (excessive topical use) Thiazide Diuretics | These agents have been associated with thyroid hormone and/or TSH level alterations by various mechanisms. |
FT4: free T4 TSH: Thyroid-stimulating hormone | |
9.5 Drug-Food Interactions
Consumption of certain foods may affect levothyroxine absorption thereby necessitating adjustments in dosing. Soybean flour (infant formula), cotton seed meal, walnuts, calcium and calcium-fortified orange juice, and dietary fibre may bind and decrease the absorption of levothyroxine sodium from the gastrointestinal tract.
9.6 Drug-Herb Interactions
St. John’s Wort may increase hepatic metabolism of levothyroxine, which may result in hypothyroidism.
9.7 Drug-Laboratory Test Interactions
A number of drugs or moieties are known to alter serum levels of TSH, T4 and T3 and may thereby influence the interpretation of laboratory tests of thyroid function (see 9 DRUG INTERACTIONS).
Changes in thyroxine-binding globulin (TBG) concentration should be taken into consideration when interpreting T4 and T3 values. Drugs such as estrogens and estrogen-containing oral contraceptives increase serum TBG concentrations. TBG concentrations may also be increased during pregnancy, in infectious hepatitis and acute intermittent porphyria. Decreases in TBG concentrations are observed in nephrosis, severe hypoproteinemia, severe liver disease, acromegaly, and after androgen or corticosteroid therapy. Familial hyper- or hypothyroxine- binding-globulinemias have been described. The incidence of TBG deficiency is approximately 1 in 9000. Certain drugs such as salicylates inhibit the protein binding of T4. In such cases, the unbound (free) hormone should be measured and/or determination of the free T4 index (FT4I) should be done.
Serum biotin may interfere with thyroid function immunoassays that are based on a biotin/streptavidin interaction, leading to either falsely decreased or falsely increased test results (see 7 WARNINGS AND PRECAUTIONS, Monitoring and Laboratory Tests).
When available, alternative tests not susceptible to biotin interference should be used for patients taking biotin-containing products.
Persistent clinical and laboratory evidence of hypothyroidism despite an adequate replacement dose suggests either poor patient compliance, impaired absorption, drug interactions, or decreased potency of the preparation due to improper storage.
10 CLINICAL PHARMACOLOGY
10.1 Mechanism of Action
The synthesis and secretion of the major thyroid hormones, T3 and T4, from the normally functioning thyroid gland are regulated by complex feedback mechanisms of the hypothalamic- pituitary-thyroid axis. The thyroid gland is stimulated to secrete thyroid hormones by the action of thyrotropin (thyroid stimulating hormone, TSH), which is produced in the anterior pituitary gland. TSH secretion is in turn controlled by thyrotropin-releasing hormone (TRH) produced in the hypothalamus, circulating thyroid hormones, and possibly other mechanisms. Thyroid hormones circulating in the blood act as feedback inhibitors of both TSH and TRH secretion.
Thus, when serum concentrations of T3 and T4 are increased, secretion of TSH and TRH decreases. Conversely, when serum thyroid hormone concentrations are decreased, secretion of TSH and TRH is increased. Administration of exogenous thyroid hormones to euthyroid individuals results in suppression of endogenous thyroid hormone secretion.
The mechanisms by which thyroid hormones exert their physiologic actions have not been completely elucidated, but it is thought that their principal effects are exerted through control of DNA transcription and protein synthesis. T3 and T4 are transported into cells by passive and active mechanisms. T3 in cell cytoplasm and T3 generated from T4 within the cell diffuse into the nucleus and bind to thyroid receptor proteins, which appear to be primarily attached to DNA. Receptor binding leads to activation or repression of DNA transcription, thereby altering the amounts of mRNA and resultant proteins. Changes in protein concentrations are responsible for the metabolic changes observed in organs and tissues.
Thyroid hormones enhance oxygen consumption of most body tissues and increase the basal metabolic rate and metabolism of carbohydrates, lipids, and proteins. Thus, they exert a profound influence on every organ system and are of particular importance in the development of the central nervous system. Thyroid hormones also appear to have direct effects on tissues, such as increased myocardial contractility and decreased systemic vascular resistance.
The physiologic effects of thyroid hormones are produced primarily by T3, a large portion of which (approximately 80%) is derived from the deiodination of T4 in peripheral tissues. About 70 to 90 percent of peripheral T3 is produced by monodeiodination of T4 at the 5 position (outer ring). Peripheral monodeiodination of T4 at the 5 position (inner ring) results in the formation of reverse triiodothyronine (rT3), which is calorigenically inactive.
Levothyroxine, at doses individualized according to patient response, is effective as replacement or supplemental therapy in hypothyroidism of any etiology, except transient hypothyroidism during the recovery phase of subacute thyroiditis.
Levothyroxine is also effective in the suppression of pituitary TSH secretion in the treatment or prevention of Hashimoto’s thyroiditis and as adjunctive therapy in the management of thyrotropin- dependent well-differentiated thyroid cancer (see 1 INDICATIONS, 7 WARNINGS AND PRECAUTIONS and 4 DOSAGE AND ADMINISTRATION).
10.3 Pharmacokinetics
Absorption:
Few clinical studies have evaluated the kinetics of orally administered thyroid hormone. In animals, the most active sites of absorption appear to be the proximal and mid- jejunum. T4 is not absorbed from the stomach and little, if any, drug is absorbed from the duodenum. There seems to be no absorption of T4 from the distal colon in animals. A number of human studies have confirmed the importance of an intact jejunum and ileum for T4 absorption and have shown some absorption from the duodenum. Studies involving radioiodinated T4 fecal tracer excretion methods, equilibration, and AUC methods have shown that absorption varies from 48 to 80 percent of the administered dose. The extent of absorption is increased in the fasting state and decreased in malabsorption syndromes, such as celiac disease (i.e., sprue, gluten-sensitive enteropathy). Absorption may also decrease with age. The degree of T4 absorption is dependent on the product formulation as well as on the character of the intestinal contents, the intestinal flora, including plasma protein and soluble dietary factors, which bind thyroid hormone, making it unavailable for diffusion. Decreased absorption may result from administration of infant soybean formula, ferrous sulfate, sodium polystyrene sulfonate, aluminum hydroxide, sucralfate, or bile acid sequestrants. T4 absorption following intramuscular administration is variable. The relative bioavailability of levothyroxine sodium tablets, compared to an equal nominal dose of oral levothyroxine sodium solution, is approximately 93%.
Distribution:
Distribution of thyroid hormones in human body tissues and fluids has not been fully elucidated. More than 99% of circulating hormones is bound to serum proteins, including thyroxine-binding globulin (TBG), thyroxine-binding prealbumin (TBPA), and albumin (TBA). T4 is more extensively and firmly bound to serum proteins than is T3. Only unbound thyroid hormone is metabolically active. The higher affinity of TBG and TBPA for T4 partly explains the higher serum levels, slower metabolic clearance, and longer serum elimination half-life of this hormone.
Certain drugs and physiologic conditions can alter the binding of thyroid hormones to serum proteins and/or the concentrations of the serum proteins available for thyroid hormone binding. These effects must be considered when interpreting the results of thyroid function tests (see 7 WARNINGS AND PRECAUTIONS, Monitoring and Laboratory Tests and 9 DRUG INTERACTIONS).
Metabolism:
The liver is the major site of degradation for both hormones. T3 and T4 are conjugated with glucuronic and sulfuric acids and excreted in the bile. There is an enterohepatic circulation of thyroid hormones, as they are liberated by hydrolysis in the intestine and reabsorbed. A portion of the conjugated material reaches the colon unchanged, is hydrolyzed there, and is eliminated as free compounds in the feces. In man, approximately 20 to 40 percent of T4 is eliminated in the stool. About 70 percent of the T4 secreted daily is deiodinated to yield equal amounts of T3 and rT3. Subsequent deiodination of T3 and rT3 yields multiple forms of diiodothyronine. A number of other minor T4 metabolites have also been identified. Although some of these metabolites have biologic activity, their overall contribution to the therapeutic effect of T4 is minimal.
Elimination:
Thyroid hormones are primarily eliminated by the kidneys. T4 is eliminated slowly from the body (see Table 6), with a half-life of 6 to 7 days. T3 has a half-life of 1 to 2 days.
Table 6 - Pharmacokinetic Parameters of Thyroid Hormones in Euthyroid Patients
| Hormone | Ratio in Thyroglobulin | Biologic Potency | t½ (days) | Protein Binding (%)2 |
| Levothyroxine, T4 | 10 to 20 | 1 | 6 to 71 | 99.96 |
| Liothyronine, T3 | 1 | 4 | ≤ 2 | 99.5 |
1 Three to four days in hyperthyroidism, nine to ten days in hypothyroidism 2 Includes TBG (thyroxine-binding globulin), TBPA (thyroxine-binding prealbumin), and TBA (thyroxine-binding albumin) | ||||
11 STORAGE, STABILITY AND DISPOSAL
Store 15°C to 25°C. Protect from light and moisture.
Keep out of reach and sight of children.
PART II: SCIENTIFIC INFORMATION
13 PHARMACEUTICAL INFORMATION
Drug Substance
Proper name: Levothyroxine sodium
Chemical name: L-Tyrosine, O-(-4-hydroxy-3,5-diiodophenyl)-3,5-diiodo-, monosodium salt, hydrate
Molecular formula and molecular mass: C15H10I4N NaO4·H2O, 798.85 g/mol (anhydrous)
Structural formula:
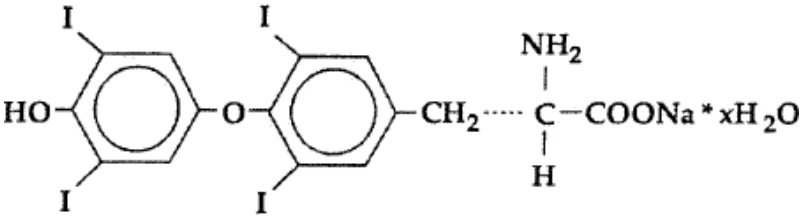
Physicochemical properties: Levothyroxine sodium occurs as an almost white or brownish yellow powder or fine, crystalline powder slightly hygroscopic. Levothyroxine sodium is slightly soluble in ethanol (96 %), it dissolves in dilute solution of alkali hydroxides and insoluble in ether at temperature 25°C ± 2°C.
14 CLINICAL TRIALS
14.1 Trial Design and Study Demographics
Table 7 - Summary of patient demographics for clinical trials in specific indication
| Author/ Manuscript Title | Study design | Dosage, route of administration and duration | Study subjects (n) | Mean age (Range) | Sex |
| Kabadi UM., 1994/ “Optimal L- thyroxine dose in primary hypothyroidism”. | Longitudinal | 25-200 mcg/day Oral dosage form | 186 | NR (25-84 years) | 152 M/34 F |
| Kabadi UM., 1989/ “Optimal L- thyroxine dose in hypothyroidism”. | Longitudinal | 50-200 mcg/day Oral dosage form | 156* | NR (25-84 years) | 133 M/23 F |
| Kabadi UM, Jackson T., 1995/ “TSH predictor in hypothyroidism”. | Longitudinal | 25-225 mcg/day Oral dosage form | 192 | NR (25-84 years) | 171 M/21 F |
| Author/ Manuscript Title | Study design | Dosage, route of administration and duration | Study subjects (n) | Mean age (Range) | Sex | |||||||
| Hennessey J, et al., 1985/ “Equivalency of two L thyroxine preparations”. | Crossover | 50-200 mcg/day Oral dosage form | 34 | NR | NR | |||||||
| Fish LH, et al., 1987/ “Replacement dose in hypothyroidism”. | Longitudinal | 25-150 mcg/day Oral dosage form | 19 | NR | NR | |||||||
| Ain KG, et al., 1996/ “Effects of restrictive formulary”. | Longitudinal | Restricted arm (n=87): 1.9 ± 0.1 mcg/kg/day Non-restricted arm (n=148): 2.0 ± 0.1 mcg/kg/day Oral dosage form | 241 | Restricted arm: (n=89): 39.3 ± 2.4 year (range NR) Non-restricted arm (n=152): 44.2 ± 1.3 year (range NR) | 74 M/167 F | |||||||
| Ain KG, et al., 1993/ “TFTs affected by time of blood sampling”. | Longitudinal | 150-200 mcg/day Oral dosage form | 51 | NR | NR | |||||||
| Liu X-Q, et al., 1998/ “Effects of L- thyroxine on serum lipoproteins”. | Longitudinal | 183 (mean) Oral dosage form | 10 | 45.7 ±10.6 year (range NR) | 2 M/8 F | |||||||
* This is considered to be an earlier publication of the same patient population presented in Kabadi, 1994. The 156 patients described are not added into the total number of patients. NR: not reported | ||||||||||||
The published studies presented in this section support the effectiveness of levothyroxine sodium in the treatment of hypothyroidism. They are considered to have at least some of the characteristics of adequate and well-controlled as defined under ICH Good Clinical Practice. The controlled clinical studies are primarily: 1) studies that investigated the biochemical response to levothyroxine sodium of patients with hypothyroidism and the correlation of the optimal clinical dose with the pathology of hypothyroidism, 2) conventional studies of untreated hypothyroid patients or those switched from another brand of the same active drug, and 3) studies that analyze the dose-response characteristics in hypothyroid patients replaced with levothyroxine sodium or patients receiving levothyroxine sodium for suppression of TSH. In all cases, objective biochemical endpoints (e.g., TSH, T4, etc.), which minimize the potential for influence of chance or bias on results, were used to assess the effectiveness of levothyroxine sodium as replacement or suppressive therapy.
14.2 Study Results
The results of the studies demonstrate that with careful dose titration to an objective, biochemical endpoint, levothyroxine sodium is effective both for initial and maintenance therapy of hypothyroid adults. On the whole, the average L-thyroxine replacement doses reported in these studies are in close agreement with each other and average replacement doses reported in the literature and recommended by thyroid experts. See 14.1 Trial Design and Study Demographics.
14.3 Comparative Bioavailability Studies
A randomized, single-dose, three-way crossover reference replicated comparative bioavailability study was conducted under fasting conditions in healthy male subjects. Serum total levothyroxine concentrations were measured, and the rate and extent of absorption were compared following a single oral dose (2 x 300 mcg) of APO-LEVOTHYROXINE (Apotex Inc.) and PrSYNTHROID® (BGP Pharma ULC). The results obtained from 47 subjects that were included in the statistical analysis are summarized in the following table.
SUMMARY TABLE OF THE COMPARATIVE BIOAVAILABILITY DATA
Total Levothyroxine (Baseline Corrected) (2 x 300 mcg Levothyroxine Sodium) Geometric Mean Arithmetic Mean (CV%) | ||||
| Parameter | Test1 | Reference2 | % Ratio of Geometric Means | 90% Confidence Interval |
AUC48 (ng·h/mL) | 1638.6 1689.9 (24.4) | 1529.4 1572.5 (22.1) | 107.14 | 102.44- 112.06 |
| Cmax (ng/mL) | 58.8 60.3 (21.6) | 55.4 56.2 (15.4) | 106.16 | 102.33- 110.13 |
| Tmax3 (h) | 3.00 (1.50-6.00) | 3.50 (1.00-10.00) | ||
1 APO- LEVOTHYROXINE (levothyroxine sodium) tablets, 300 mcg (Apotex Inc.) 2 SYNTHROID® Tablets (levothyroxine sodium) tablets, 300 mcg (BGP Pharma ULC) was purchased in Canada. 3 Expressed as the median (range) only Note: Due to the long elimination half-life of levothyroxine, AUCI and T1/2 could not be accurately calculated from the data obtained in this study | ||||
A randomized, single-dose, three-way crossover reference replicated comparative bioavailability study was conducted under fed conditions in healthy male subjects. Serum total levothyroxine concentrations were measured, and the rate and extent of absorption were compared following a single oral dose (2 x 300 mcg) of APO-LEVOTHYROXINE (Apotex Inc.) and PrSYNTHROID® (BGP Pharma ULC). The results obtained from 47 subjects that were included in the statistical analysis are summarized in the following table.
SUMMARY TABLE OF THE COMPARATIVE BIOAVAILABILITY DATA
Total Levothyroxine (Baseline Corrected) (2 x 300 mcg Levothyroxine Sodium) Geometric Mean Arithmetic Mean (CV%) | ||||
| Parameter | Test1 | Reference2 | % Ratio of Geometric Means | 90% Confidence Interval |
AUC0-48 (ng·h/mL) | 1090.1 1135.3 (26.7) | 1048.4 1090.6 (25.6) | 104.0 | 98.3- 110.0 |
| Cmax (ng/mL) | 35.3 36.8 (25.6) | 36.5 37.6 (23.2) | 96.8 | 92.0- 101.8 |
| Tmax3 (h) | 4.50 (2.50-24.00) | 4.50 (1.50-24.00) | ||
1 APO- LEVOTHYROXINE (levothyroxine sodium) tablets, 300 mcg (Apotex Inc.) 2 SYNTHROID® Tablets (levothyroxine sodium) tablets, 300 mcg (BGP Pharma ULC) was purchased in Canada. 3 Expressed as the median (range) only Note: Due to the long elimination half-life of levothyroxine, AUCI and T1/2 could not be accurately calculated from the data obtained in this study. | ||||
A randomized, single-dose, three-way crossover reference replicated comparative bioavailability study was conducted under fasting conditions in healthy male subjects. Serum total levothyroxine concentrations were measured, and the rate and extent of absorption were compared following a single oral dose (6 x 100 mcg) of APO- LEVOTHYROXINE (Apotex Inc.) and PrSYNTHROID® (BGP Pharma ULC). The results obtained from 48 subjects that were included in the statistical analysis are summarized in the following table.
SUMMARY TABLE OF THE COMPARATIVE BIOAVAILABILITY DATA
Total Levothyroxine (Baseline Corrected) (6 x 100 mcg Levothyroxine Sodium) Geometric Mean Arithmetic Mean (CV%) | ||||
| Parameter | Test1 | Reference2 | % Ratio of Geometric Means | 90% Confidence Interval |
AUC0-48 (ng·h/mL) | 1744.5 1774.9 (19.4) | 1714.1 1747.0 (21.2) | 101.8 | 97.9- 105.8 |
| Cmax (ng/mL) | 62.0 63.0 (18.7) | 61.6 62.7 (19.7) | 100.6 | 97.5- 103.9 |
| Tmax3 (h) | 3.00 (1.50-12.00) | 3.00 (1.50-12.00) | ||
1 APO- LEVOTHYROXINE (levothyroxine sodium) tablets, 100 mcg (Apotex Inc.) 2 SYNTHROID® Tablets (levothyroxine sodium) tablets, 100 mcg (BGP Pharma ULC) was purchased in Canada. 3 Expressed as the median (range) only Note: Due to the long elimination half-life of levothyroxine, AUCI and T1/2 could not be accurately calculated from the data obtained in this study. | ||||
15 MICROBIOLOGY
No microbiological information is required for this drug product.
16 NON-CLINICAL TOXICOLOGY
This information is not available for this drug product.
17 SUPPORTING PRODUCT MONOGRAPHS
- 1. SYNTHROID® (tablets, 25 mcg, 50 mcg, 75 mcg, 88 mcg, 100 mcg, 112 mcg, 125 mcg, 137 mcg, 150 mcg, 175 mcg, 200 mcg and 300 mcg), submission control 275351, Product Monograph, BGP Pharma ULC. (AUG 17, 2023)