Product Monograph - Apo-Naltrexone
ACTION AND CLINICAL PHARMACOLOGY
Pharmacodynamic Actions
APO-NALTREXONE (naltrexone hydrochloride) is a pure opioid antagonist. It markedly attenuates or completely blocks, reversibly, the subjective effects of intravenously administered opioids. [In this context, the term opioid is used to describe 1) classic morphine-like agonists and 2) analgesics possessing agonist and antagonist activity (eg, butorphanol, nalbuphine and pentazocine)].
When co-administered with morphine, on a chronic basis, naltrexone hydrochloride blocks the physical dependence to morphine and presumably other opioids. Naltrexone hydrochloride has few, if any, intrinsic actions besides its opioid blocking properties. However, it does produce some pupillary constriction, by an unknown mechanism.
While the mechanism of action is not fully understood, the preponderance of evidence suggests that naltrexone hydrochloride blocks the effects of opioids by competitive binding (ie, analogous to competitive inhibition of enzymes) at opioid receptors. This makes the blockade produced potentially surmountable, but overcoming full naltrexone blockade by administration of very high doses of opiates has resulted in excessive symptoms of histamine release in experimental subjects.
The mechanism of action of naltrexone hydrochloride in the treatment of alcoholism is not understood; however, involvement of the endogenous opioid system is suggested by preclinical data. Naltrexone hydrochloride, an opioid receptor antagonist, competitively binds to such receptors and may block the effects of endogenous opioids. Opioid antagonists have been shown to reduce alcohol consumption by animals, and naltrexone hydrochloride has been shown to reduce alcohol consumption in clinical studies.
Naltrexone hydrochloride is not aversive therapy and does not cause a disulfiram-like reaction either as a result of opiate use or ethanol ingestion.
The administration of naltrexone hydrochloride is not associated with the development of tolerance or dependence.
In subjects physically dependent on opioids, naltrexone hydrochloride will precipitate withdrawal symptomatology.
Clinical studies indicate that 50 mg of naltrexone hydrochloride will block the pharmacologic effects of 25 mg of intravenously administered heroin for periods as long as 24 hours. Other data suggest that doubling the dose of naltrexone hydrochloride provides blockade for 48 hours, and tripling the dose of naltrexone hydrochloride provides blockade for about 72 hours.
Pharmacokinetics/Bioavailability
Following oral administration, naltrexone hydrochloride undergoes rapid and nearly complete absorption with approximately 96% of the dose absorbed from the gastrointestinal tract. Although well absorbed orally, naltrexone is subject to extensive "first-pass" hepatic metabolism with an oral bioavailability estimate ranging from 5 to 40%. The activity of naltrexone is believed to be due to both parent and the 6-β-naltrexol metabolite.
Following the administration of 50 mg naltrexone hydrochloride tablets to 24 healthy adult male volunteers, the Cmax for naltrexone hydrochloride and its major metabolite, 6-β-naltrexol were 8.6 ng/mL and 99.3 ng/mL, respectively. The maximum concentration (Cmax) and area under the curve (AUC), for both naltrexone and 6-β-naltrexol are dose proportional over the range of 50 to 200 mg. The time to maximum concentration (Tmax) is one hour for both naltrexone and 6-β-naltrexol. The mean elimination half-life (T1/2) values for naltrexone and 6-β-naltrexol are 4 hours and 12.9 hours, respectively. The mean elimination half-life (T1/2) and time to maximum concentration (Tmax) for naltrexone hydrochloride and 6-β-naltrexol are independent of dose.
The volume of distribution for naltrexone hydrochloride following intravenous administration is estimated to be 1,350 litres. In vitro tests with human plasma show naltrexone to be 21% bound to plasma protein over the therapeutic dose range.
The systemic clearance (after intravenous administration) of naltrexone hydrochloride approximates 3.5 L/min, which exceeds liver blood flow (-1.35 L/min), and suggests that naltrexone hydrochloride is a highly extracted drug (>98% metabolized) and that extrahepatic sites of drug metabolism exist. The major metabolite of naltrexone is 6-β-naltrexol. Two other minor metabolites are 2-hydroxy-3- methoxy- 6-β-naltrexol and 2-hydroxy-3-methyl-naltrexone. Naltrexone and its metabolites are also conjugated to form additional metabolic products. A renal clearance ranging from 30 to 127 mL/min for naltrexone suggests it is primarily cleared by glomerular filtration. A renal clearance of 230 to 369 mL/min for 6-β-naltrexol suggests an additional renal tubular secretory mechanism. Naltrexone hydrochloride and its metabolites are excreted primarily by the kidney (56% to 79% of the dose), with fecal excretion being a minor elimination pathway. The urinary excretion of unchanged naltrexone hydrochloride accounts for less than 2% of an oral dose; urinary excretion of unchanged and conjugated 6-β-naltrexol accounts for approximately 43% of an oral dose. The pharmacokinetic profile of naltrexone hydrochloride suggests that naltrexone hydrochloride and its metabolites undergo enterohepatic recycling.
Adequate studies of naltrexone in patients with severe hepatic or renal impairment have not been conducted; however, a recent preliminary communication stated that naltrexone bioavailability is increased in patients with liver cirrhosis as compared to healthy subjects (see PRECAUTIONS: Special Risk Patients).
CLINICAL TRIALS
Apo-Naltrexone 50 mg tablets have satisfied the criteria for a Biopharmaceutics Classification System (BCS)-based biowaiver in comparison to the Canadian Reference Product, Revia® 50 mg tablets (Teva Canada Limited).
Treatment of Opioid Addiction
Naltrexone hydrochloride has been shown to produce complete blockade of the euphoric effects of opioids in both volunteer and addict populations. When administered by means that enforce compliance, it will produce an effective opioid blockade, but has not been shown to affect the use of cocaine or other nonopioid drugs of abuse.
The drug is reported to be of greatest use in good prognosis opioid addicts who take the drug as part of a comprehensive occupational rehabilitative program, behavioural contract, or other compliance enhancing protocols.
Alcoholism
The efficacy of naltrexone hydrochloride as an aid to the treatment of alcoholism was tested in placebo-controlled, outpatient, double-blind trials. These studies used a dose of naltrexone hydrochloride 50 mg once daily for 12 weeks as an adjunct to social and psychotherapeutic methods. Patients with psychosis, dementia, and secondary psychiatric diagnosis were excluded from these studies.
In one of these studies, 104 alcohol-dependent patients were randomized to receive either naltrexone hydrochloride 50 mg once daily or placebo. In this study, naltrexone hydrochloride proved superior to placebo in measures of drinking including abstention rates (51% vs. 23%), number of drinking days, and relapse rates (31% vs. 60%). In a second study with 82 alcohol-dependent patients, the group of patients receiving naltrexone hydrochloride were shown to have lower relapse rates (21% vs. 41%), less alcohol craving, and fewer drinking days compared with patients who received placebo.
The clinical use of naltrexone hydrochloride as adjunctive pharmacotherapy for the treatment of alcoholism was also evaluated in a multicenter safety study. This study of 865 individuals with alcoholism included patients with comorbid psychiatric conditions, concomitant medications, polysubstance abuse and HIV disease. Results of this study demonstrated that the side-effect profile of naltrexone hydrochloride appears to be similar in both alcoholic and opioid dependent populations.
Naltrexone hydrochloride was not uniformly helpful to all patients, and the expected effect of the drug is a modest improvement in the outcome of conventional treatment.
INDICATIONS AND CLINICAL USE
APO-NALTREXONE (naltrexone hydrochloride) is indicated to provide blockade of the pharmacologic effects of exogenously administered opioids as an adjunct to the maintenance of the opioid-free state in detoxified, formerly opioid-dependent individuals. There are no data that demonstrate an unequivocally beneficial effect of APO-NALTREXONE on the rates of recidivism among detoxified formerly opioid-dependent individuals, who self administer the drug. APO-NALTREXONE is expected to have a therapeutic effect only when given under conditions that support continued use of the medication.
APO-NALTREXONE is indicated in the treatment of alcohol dependence, as a component of a comprehensive psychotherapeutic or psychological alcoholism counselling program to support abstinence, and reduce the risk of relapse. The efficacy of APO-NALTREXONE beyond twelve weeks of treatment has not been established.
CONTRAINDICATIONS
APO-NALTREXONE is contraindicated in:
- 1. Patients receiving opioid analgesics.
- 2. Patients currently dependent on opioids, including those currently maintained on opiate agonists [eg. Methadone or LAAM (levo-alpha-acetyl-methadol)].
- 3. Patients in acute opioid withdrawal (see WARNINGS).
- 4. Any individual who has failed the NARCAN* challenge (see DOSAGE AND ADMINISTRATION Section).
- 5. Any individual who has a positive urine screen for opioids.
- 6. Any individual with a history of sensitivity to APO-NALTREXONE or any other components of this product (see PHARMACEUTICAL INFORMATION: Composition). It is not known if there is any cross-sensitivity with naloxone or other phenanthrene containing opioids.
- 7. Any individual with acute hepatitis or liver failure.
WARNINGS
Unintended Precipitation of Withdrawal
To prevent occurrence of an acute withdrawal syndrome, or exacerbation of a pre-existing sub-clinical withdrawal syndrome, patients should remain opioid-free for a minimum of 7-10 days before starting APO-NALTREXONE. Since the absence of an opioid drug in the urine often is not sufficient proof that the patient is opioid-free, a NARCAN* challenge may be required to minimize the possibility of precipitating a withdrawal reaction following administration of APO-NALTREXONE. The NARCAN* challenge test is described in the DOSAGE AND ADMINISTRATION Section.
Hepatotoxicity
APO-NALTREXONE has the capacity to cause dose related hepatocellular injury. Prior to making a decision to initiate treatment with APO-NALTREXONE, the physician should establish whether the patient has subclinical liver injury or disease (see PRECAUTIONS: Laboratory Tests). APO-NALTREXONE is contraindicated in acute hepatitis or liver failure, and its use even in patients with evidence of less severe liver disease or a history of recent liver disease must be carefully considered in light of its hepatotoxic potential.
The evidence that identified naltrexone hydrochloride as a hepatotoxin was not obtained in studies involving its use at the doses recommended for opiate blockade, or for treatment of alcohol dependence (50 mg/day). However, the margin of separation between the apparently safe and the hepatotoxic doses appears to be only five-fold or less.
Patients should be warned of the risk of hepatic injury and advised to stop the use of APO-NALTREXONE and seek medical attention if they experience symptoms of acute hepatitis.
Evidence of the hepatotoxic potential of naltrexone hydrochloride is derived primarily from a placebo controlled study in which naltrexone hydrochloride was administered to obese subjects at a dose approximately five-fold that recommended for the blockade of opiate receptors (300 mg/day). In the study, 5 of 26 naltrexone hydrochloride recipients developed elevations of serum transaminases (ie, peak ALT values ranging from a low of 121 to a high of 532, or 3 to 19 times their baseline values) after three to eight weeks of treatment. Although the patients involved were generally clinically asymptomatic and the transaminase levels of all patients on whom follow-up was obtained returned to (or toward) baseline values in a matter of weeks, the lack of any transaminase elevations of similar magnitude in any of the 24 placebo patients in the same study is persuasive evidence that naltrexone hydrochloride is a direct (ie, not an idiosyncratic) hepatotoxin. This conclusion is also supported by evidence from other placebo controlled studies in which exposure to naltrexone hydrochloride at doses from one to two-fold the amount recommended for the treatment of alcoholism or opiate blockade (50 mg/day) consistently produced more numerous and more significant elevations of serum transaminase than did placebo, and reports of transaminase elevations in 3 of 9 patients with Alzheimer's Disease who received naltrexone hydrochloride (up to 300 mg/day) for 5 to 8 weeks in an open clinical trial have been reported.
Although no cases of hepatic failure due to naltrexone hydrochloride administration have ever been reported, physicians are advised to consider this as a possible risk of treatment and to use the same care in prescribing APO-NALTREXONE as they would other drugs with the potential for causing hepatic injury.
Attempt to Overcome Blockade
While APO-NALTREXONE is a potent antagonist with a prolonged pharmacologic effect (24 to 72 hours), the blockade produced by APO-NALTREXONE is surmountable. This is useful in patients who may require analgesia, but poses a potential risk to individuals who attempt, on their own, to overcome the blockade by administering large amounts of exogenous opioids. Indeed, any attempt by a patient to overcome the antagonism by taking opioids is very dangerous and may lead to a fatal overdose. Injury may arise because the plasma concentration of exogenous opioids attained immediately following their acute administration may be sufficient to overcome the competitive receptor blockade. As a consequence, the patient may be in immediate danger of suffering life endangering opioid intoxication (eg, respiratory arrest, circulatory collapse). Patients should be told of the serious consequences of surmounting the opiate blockade. (See INFORMATION FOR THE CONSUMER)
There is also the possibility that a patient who had been treated with naltrexone will respond to lower doses of opioids than previously used, particularly if taken in such a manner that high plasma concentrations remain in the body beyond the time that naltrexone exerts its therapeutic effects. This could result in potentially life-threatening opioid intoxification (respiratory compromise or arrest, circulatory collapse, etc.). Patients should be aware that they may be more sensitive to lower doses of opioids after naltrexone treatment is discontinued.
PRECAUTIONS
General
Emergency Pain Management in Patients Receiving Fully Blocking Doses of APO-NALTREXONE
In an emergency situation in patients receiving fully blocking doses of APO-NALTREXONE, a suggested plan of management is regional analgesia, conscious sedation with a benzodiazepine, use of non- opioid analgesics or general anesthesia. In a situation requiring analgesia which can only be achieved with opioids, the amount of opioid required may be greater than usual, and the resulting respiratory depression may be deeper and more prolonged. In such circumstances, a rapidly acting opioid analgesic which minimizes the duration of respiratory depression is preferred. The amount of analgesic administered should be titrated to the needs of the patient. No methods to reverse opioid overdose in patient's receiving naltrexone have been established by clinical trials. However, the use of the opioid antagonist naloxone, should be considered when attempting reversal.
Additionally, non-receptor mediated actions may occur (e.g., facial swelling, itching, generalized erythema, presumably due to histamine release). Irrespective of the drug chosen to reverse APO-NALTREXONE blockade, the patient should be monitored closely by appropriately trained personnel in
a hospital setting equipped and staffed for cardiopulmonary resuscitation.
Interference with the Action of Opioid Containing Drug Product
Patients taking APO-NALTREXONE may not benefit from opioid containing medicines, such as cough and cold preparations, antidiarrheal preparations, and opioid analgesics. Where a non-opioid containing alternative is available, it should be used.
Accidentally Precipitated Withdrawal
Severe opioid withdrawal syndromes precipitated by the accidental ingestion of naltrexone hydrochloride have been reported in opioid-dependent individuals. Symptoms of withdrawal have usually appeared within five minutes of ingestion of naltrexone hydrochloride and have lasted for up to 48 hours. Mental status changes including confusion, somnolence and visual hallucinations have occurred. Significant fluid losses from vomiting and diarrhea have required intravenous fluid administration. In all cases patients were closely monitored and therapy tailored to meet individual requirements.
Use of APO-NALTREXONE does not eliminate or diminish withdrawal symptoms. If APO-NALTREXONE is initiated early in the abstinence process, it will not preclude the patients's experience of the full range of signs and symptoms that would be experienced if APO-NALTREXONE had not been started. Numerous adverse events are known to be associated with withdrawal.
Special Risk Patients
Renal Impairment: APO-NALTREXONE and its primary metabolite are excreted primarily in the urine, and caution is recommended in administering the drug to patients with renal impairment.
Hepatic Impairment: Caution should be exercised when naltrexone hydrochloride is administered to patients with liver disease. An increase in naltrexone AUC of approximately 5- and 10-fold in patients with compensated and decompensated liver cirrhosis, respectively, compared with subjects with normal liver function has been reported. These data also suggest that alterations in naltrexone bioavailability are related to liver disease severity.
Drug Interactions
Studies to evaluate possible interactions between APO-NALTREXONE and drugs other than opiates have not been performed. Consequently, caution is advised if the concomitant administration of APO-NALTREXONE and other drugs is required.
The safety and efficacy of concomitant use of APO-NALTREXONE and disulfiram is unknown, and the concomitant use of two potentially hepatotoxic medications is not ordinarily recommended unless the probable benefits outweigh the known risks.
Lethargy and somnolence have been reported following doses of naltrexone hydrochloride and thioridazine.
Suicide
The risk of suicide is known to be increased in patients with substance abuse with or without concomitant depression. The risk is not abated by treatment with APO-NALTREXONE (see ADVERSE REACTIONS).
Laboratory Tests
Tests designed to detect hepatic injury should be obtained prior to initiation of APO-NALTREXONE therapy and periodically thereafter (see WARNINGS Section on Hepatotoxicity).
Periodic testing of all patients after initiation of treatment is critical if the occurrence of APO-NALTREXONE induced liver damage is to be detected at the earliest possible time. Evaluations, using appropriate batteries of tests to detect liver injury are recommended on a monthly basis during the first six months of use; thereafter, clinical judgement about the frequency of monitoring must be relied upon.
Laboratory tests which may be used for the separation and detection of morphine, methadone, or quinine in the urine and with which APO-NALTREXONE does not interfere include thin-layer, gas-liquid, and high pressure liquid chromatographic methods.
Impairment of Fertility
Naltrexone hydrochloride (100 mg/kg, approximately 100 times the human therapeutic dose) caused a significant increase in pseudopregnancy in the rat. A decrease in the pregnancy rate of mated female rats also occurred. The relevance of these observations to human fertility is not known.
Use in Pregnancy
There are no adequate and well-controlled studies in pregnant women. APO-NALTREXONE should be used in pregnancy only when the potential benefits justify the potential risk to the fetus. Naltrexone hydrochloride has been shown to have embryocidal and fetotoxic effects in rats and rabbits when given in dosages 30 and 60 times, respectively, the human dose.
Labour and Delivery
It is not known whether APO-NALTREXONE affects the duration of labour and delivery.
Nursing Mothers
It is not known whether APO-NALTREXONE is excreted in human milk. Because many drugs are excreted in human milk, APO-NALTREXONE should be administered to a nursing mother only when the potential benefits justify the potential risk to the infant.
Pediatric Use
The safe use of APO-NALTREXONE in subjects younger than 18 years of age has not been established.
ADVERSE REACTIONS
While extensive clinical studies evaluating the use of naltrexone hydrochloride in detoxified, formerly opioid dependent individuals failed to identify any single, serious untoward risk of naltrexone hydrochloride use, placebo controlled studies employing up to five-fold higher doses of naltrexone hydrochloride (up to 300 mg/day) than that recommended for use in opiate receptor blockade have shown that naltrexone hydrochloride caused hepatocellular injury in 5 of 26 patients exposed at this higher dose (see WARNINGS and PRECAUTIONS: Laboratory Tests).
Aside from this finding, however, available evidence does not incriminate naltrexone hydrochloride, used at any dose, as a cause of any other serious untoward event for the patient who is "opioid free". It is critical to recognize that APO-NALTREXONE can precipitate or exacerbate withdrawal signs and symptoms in any individual who is not completely free of exogenous opioids (see CONTRAINDICATIONS, WARNINGS, DOSAGE AND ADMINISTRATION).
Opioid Withdrawal-like Symptoms
Studies in alcoholic populations and in volunteers in clinical pharmacology studies have suggested that a small fraction of patients may experience an opioid withdrawal-like symptom complex consisting of tearfulness, mild nausea, abdominal cramps, restlessness, bone or joint pain, myalgia, and nasal symptoms. This may represent the unmasking of occult opioid use, or it may represent symptoms attributable to naltrexone. A number of alternative dosing patterns have been recommended to try to reduce the frequency of these complaints (see Individualization of Dosage).
Opioid Addiction
Events Other than Hepatocellular Injury Reported During Clinical Testing: The following adverse reactions have been reported both at baseline and during the naltrexone hydrochloride clinical trials in opioid addiction at an incidence rate of more than 10%: Difficulty sleeping, anxiety, nervousness, abdominal pain/cramps, nausea and/or vomiting, low energy, joint and muscle pain, and headache.
The incidence was less than 10% for: Loss of appetite, constipation, increased thirst, increased energy, feeling down, irritability, dizziness, skin rash, delayed ejaculation, decreased potency, and chills.
The following events occurred in less than 1% of subjects:
Respiratory: nasal congestion, itching, rhinorrhea, sneezing, sore throat, excess mucus or phlegm, sinus trouble, heavy breathing, hoarseness, cough, shortness of breath.
Cardiovascular: nose bleeds, phlebitis, edema, increased blood pressure, non-specific EGG changes, palpitations, tachycardia.
Gastrointestinal: excessive gas, haemorrhoids, diarrhea, ulcer.
Musculoskeletal: painful shoulders, legs or knees, tremors, twitching.
Genitourinary: increased frequency of, or discomfort during urination, increased or decreased sexual interest.
Dermatologic: oily skin, pruritus, acne, athlete's foot, cold sore, alopecia.
Psychiatric: depression, paranoia, fatigue, restlessness, confusion, disorientation, hallucinations, nightmares, bad dreams.
Special Senses: eyes- blurred, burning, light sensitive, swollen, aching, strained; ears- "clogged", aching, tinnitus.
General: increased appetite, weight loss, weight gain, yawning, somnolence, fever, dry mouth, head "pounding", inguinal pain, swollen glands, "side" pains, cold feet, "hot spells".
Post-marketing Experience
Data collected from post-marketing use of naltrexone hydrochloride show that most events usually occur early in the course of drug therapy and are transient. It is not always possible to distinguish these occurrences from those signs and symptoms that may result from a withdrawal syndrome. Events that have been reported include anorexia, asthenia, chest pain, fatigue, headache, hot flushes, malaise, changes in blood pressure, agitation, dizziness, hyperkinesia, nausea, vomiting, tremor, abdominal pain, diarrhea, elevations in liver enzymes or bilirubin, hepatic function abnormalities or hepatitis, palpitations, myalgia, anxiety, confusion, euphoria, hallucinations, insomnia, nervousness, somnolence, abnormal thinking, dyspnea, rash, increased sweating, and vision abnormalities.
Depression, suicide, attempted suicide and suicidal ideation have been reported in the post-marketing experience with naltrexone hydrochloride used in the treatment of opioid dependence. No causal relationship has been demonstrated. In the literature, endogenous opioids have been theorized to contribute to a variety of conditions. In some individuals the use of opioid antagonists has been associated with a change in baseline levels of some hypothalamic, pituitary, or gonadal hormones. The clinical significance of such changes is not fully understood.
Laboratory Tests
With the exception of liver test abnormalities in investigator studies (see WARNINGS, PRECAUTIONS), results of laboratory tests, like adverse reports, have not shown consistent patterns of abnormalities that can be attributed to treatment with naltrexone hydrochloride.
In the trials evaluating naltrexone hydrochloride for the blockade of opiate receptors, abnormal liver function tests and lymphocytosis were the two most common categories of abnormalities reported. These abnormalities are common among populations of parenteral opioid users and alcoholics. As is the case with the untoward events described above, a large proportion of patients had abnormal tests at baseline, further supporting the conclusion that the abnormalities observed are not attributable to naltrexone hydrochloride.
Idiopathic thrombocytopenic purpura was reported in one patient who may have been sensitized to naltrexone hydrochloride in a previous course of treatment with naltrexone hydrochloride. The condition cleared without sequelae after discontinuation of naltrexone hydrochloride and corticosteroid treatment.
Alcoholism
In two randomized, double-blind placebo controlled 12 week trials to evaluate the efficacy of naltrexone hydrochloride as adjunctive treatment of alcohol dependence, a total of 93 patients received naltrexone hydrochloride at a dose of 50 mg once daily. The most common (incidence greater than 10%) adverse events associated with the use of naltrexone hydrochloride in these trials (incidence at least 5% greater than in patients receiving placebo} were: somnolence, nervousness, vomiting, weight decrease, dry mouth and decreased libido. The incidences of adverse events leading to discontinuation of naltrexone hydrochloride in these trials were: vomiting (5%); agitation (2%); insomnia (2%); nervousness (1%); drowsiness (1%); and malaise (1%). Discontinuation rate for headache was 1% for patients on naltrexone and 2% for patients on placebo. No serious adverse events were reported during these two trials.
| In an open label safety study with approximately 570 individuals with alcoholism receiving naltrexone, the following new onset adverse reactions occurred in 2% or more of the patients: | In an open label safety study with approximately 570 individuals with alcoholism receiving naltrexone, the following adverse events were responsible for discontinuation in ≥ 1% of patients: | ||||||||||||
| Adverse Reaction | Percent (%) | Adverse Reaction | Incidence of Discontinuation | ||||||||||
| Nausea | 10% | Nausea | 6% | ||||||||||
| Headache | 7% | Headache | 3% | ||||||||||
| Dizziness | 4% | Dizziness | 3% | ||||||||||
| Nervousness | 4% | Anxiety | 2% | ||||||||||
| Fatigue | 4% | Nervousness | 2% | ||||||||||
| Insomnia | 3% | Fatigue | 1% | ||||||||||
| Vomiting | 3% | Vomiting | 1% | ||||||||||
| Anxiety | 2% | Depression | 1% | ||||||||||
| Somnolence | 2% | Euphoria | 1% | ||||||||||
| Dry Mouth | 2% | Mouth Dry | 1% | ||||||||||
| Dyspepsia | 2% | Insomnia | 1% | ||||||||||
Depression, suicidal ideation, and suicidal attempts have been reported in all groups when comparing naltrexone, placebo, or controls undergoing treatment for alcoholism.
Rate Ranges of New Onset Events
| New Onset Event | Naltrexone | Placebo |
| Depression | 0 to 15% | 0 to 17% |
| Suicide Attempt/Ideation | 0 to 1% | 0 to 3% |
Although no causal relationship with naltrexone hydrochloride is suspected, physicians should be aware that treatment with APO-NALTREXONE does not reduce the risk of suicide in these patients (see PRECAUTIONS).
DRUG ABUSE AND DEPENDENCE
APO-NALTREXONE is a pure opioid antagonist. It does not lead to physical or psychological dependence. Tolerance to the opioid antagonist effect is not known to occur.
SYMPTOMS AND TREATMENT OF OVERDOSAGE
| For management of a suspected drug overdose contact your regional Poison Control Centre. |
Symptoms
There is limited clinical experience with naltrexone hydrochloride overdosage in humans. In one study, subjects who received 800 mg daily naltrexone hydrochloride for up to one week showed no evidence of toxicity.
Treatment
Consideration should be given to contacting a poison control center for the most up-to-date information. In view of the lack of actual experience in the treatment of APO-NALTREXONE overdose, patients should be treated symptomatically in a closely supervised environment.
DOSAGE AND ADMINISTRATION
Initiation of APO-NALTREXONE Therapy
DO NOT ATTEMPT TREATMENT WITH APO-NALTREXONE UNLESS, IN THE MEDICAL JUDGEMENT OF THE PRESCRIBING PHYSICIAN, THERE IS NO REASONABLE POSSIBILITY OF OPIOID USE WITHIN THE PAST 7-10 DAYS. IF THERE IS ANY QUESTION OF OCCULT OPIOID DEPENDENCE, PERFORM A NARCAN CHALLENGE TEST AND DO NOT ATTEMPT TO INITIATE APO-NALTREXONE THERAPY UNTIL NARCAN* CHALLENGE IS NEGATIVE (see below).
Treatment of Opioid Dependence
Initiate treatment with APO-NALTREXONE using the following guidelines:
- 1. Treatment should not be attempted until the patient has remained opioid-free for 7 to 10 days. Self-reporting of abstinence from opioids should be verified by analysis of the patient's urine for absence of opioids. The patient should not be manifesting withdrawal signs or reporting withdrawal symptoms.
- 2. If there is any question of occult opioid dependence perform a NARCAN* challenge test (see below). If signs of opioid withdrawal are still observed following NARCAN* challenge, treatment with APO-NALTREXONE should not be attempted. The NARCAN* challenge can be repeated in 24 hours.
- 3. Treatment should be initiated carefully, slowly increasing the dose of APO-NALTREXONE administered.
This can be accomplished by administration of 25 mg of APO-NALTREXONE initially. The patient should be observed for 1 hour. If no withdrawal signs occur, the patient may be given the rest of the daily dose.
Once the patient has been started on APO-NALTREXONE, 50 mg every 24 hours will produce adequate clinical blockade of the actions of parenterally administered opioids (i.e., this dose will block the effects of a 25 mg intravenous heroin challenge). A flexible approach to a dosing regimen may be employed in cases of supervised administration. Thus, patients may receive 50 mg of APO-NALTREXONE every weekday with a 100 mg dose on Saturday or patients may receive 100 mg every other day, or 150 mg every third day. While the degree of opioid blockade may be somewhat reduced by using higher doses at longer dosing intervals, improved patient compliance may result from dosing every 48 to 72 hours.
Several of the clinical studies reported in the literature have employed the following dosing regimen: 100 mg on Monday, 100 mg on Wednesday, and 150 mg on Friday. This dosing schedule appeared to be acceptable to many naltrexone patients successfully maintaining their opioid free state.
Treatment of Alcoholism
A dose of 50 mg once daily is recommended.
The placebo-controlled studies that demonstrated the efficacy of naltrexone hydrochloride as an adjunctive treatment of alcoholism used a dose regimen of naltrexone hydrochloride 50 mg once daily for up to 12 weeks. Other dose regimens or durations of therapy were not evaluated in these trials.
A patient is a candidate for treatment with APO-NALTREXONE if:
- the patient is willing to take a medicine to help with alcohol dependence;
- the patient is opioid free for 7 to 10 days;
- the patient does not have severe or active liver or kidney problems (typical guidelines suggest liver function tests no greater than three times the upper limits of normal, and bilirubin normal); and
- the patient is not allergic to APO-NALTREXONE, and no other contraindications are present.
Refer to CONTRAINDICATIONS, WARNINGS, and PRECAUTIONS for additional information.
APO-NALTREXONE should be used as part of a comprehensive treatment program for alcohol dependence. Factors associated with a good outcome include: appropriate management of comorbid conditions; use of community-based support groups; and good medication compliance. To achieve the best possible treatment outcome, appropriate compliance enhancing techniques should be implemented for all components of the treatment program, especially medication compliance.
The efficacy of APO-NALTREXONE beyond twelve weeks of treatment has not been established.
NARCAN* CHALLENGE TEST
The NARCAN* challenge test should not be performed in a patient showing clinical signs or symptoms of opioid withdrawal, or in a patient whose urine contains opioids. The NARCAN* challenge test may be administered by either the intravenous or subcutaneous routes.
Intravenous: Inject 0.5 mL (0.2 mg) NARCAN* (0.4 mg/mL). Observe patient for 30 seconds for signs or symptoms of withdrawal. If there is no evidence of withdrawal, inject another 1.5 mL (0.6 mg) of NARCAN*. Observe patient for an additional 20 minutes.
Subcutaneous: Administer 2 mL (0.8 mg) NARCAN* (0.4 mg/mL). Observe patient for 20 minutes for signs or symptoms of withdrawal.
Note: Individual patients, especially those with opioid dependence, may respond to lower doses of NARCAN*. In some cases, 0.25 mL (0.1 mg) intravenous NARCAN* (0.4 mg/mL) has produced a diagnostic response.
Interpretation of the Challenge: Monitor vital signs and observe the patient for signs and symptoms of opioid withdrawal. These may include, but are not limited to: nausea, vomiting, dysphoria, yawning, sweating, tearing, rhinorrhea, stuffy nose, craving for opioids, poor appetite, abdominal cramps, sense of fear, skin erythema, disrupted sleep patterns, fidgeting, uneasiness, poor ability to focus, mental lapses, muscle aches or cramps, pupillary dilation, piloerection, fever, changes in blood pressure, pulse or temperature, anxiety, depression, irritability, back ache, bone or joint pains, tremors, sensations of skin crawling or fasciculations. If signs or symptoms of withdrawal appear, the test is positive and no additional NARCAN* should be administered.
Warning: If the test is positive, do NOT initiate APO-NALTREXONE therapy. Repeat the challenge in 24 hours (see Confirmatory rechallenge). If the test is negative, APO-NALTREXONE therapy may be started if no other contraindications are present. If there is any doubt about the result of the test, withhold APO-NALTREXONE and repeat the challenge in 24 hours (see Confirmatory rechallenge).
Confirmatory rechallenge (if necessary): Four (4) mL (1.6 mg) of NARCAN* (0.4 mg/mL) should be injected intravenously and the patient again observed for signs and symptoms of withdrawal. If none are present, APO-NALTREXONE may be administered. If signs and symptoms of withdrawal are present, administration of APO-NALTREXONE should be delayed until repeated NARCAN* challenge indicates the patient is no longer at risk.
PHARMACEUTICAL INFORMATION
Drug Substance
Proper Name: Naltrexone Hydrochloride
Chemical Names: 1) Morphinan-6-one, 17-(cyclopropylmethyl)-4,5-epoxy-3, 14 dihydroxy,(5α)-
2)17-(Cyclopropylmethyl)-4,5ɑ-epoxy-3, 14-dihydroxymorphinan-6- one hydrochloride
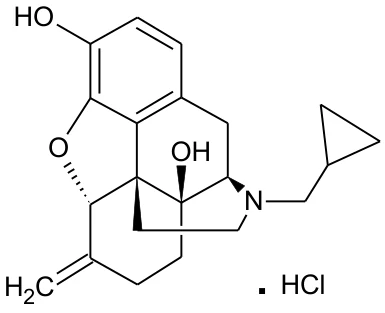
Structural Formula:
Molecular Formula: C20H23NO4•HCl
Molecular Weight: 377.86
Description: Naltrexone hydrochloride is a white or almost white powder.
Solubility: Freely soluble in water, slightly soluble in ethanol (96%), practically insoluble in methylene chloride.
pKa Value: 8.13, 8.73
pH: 5.17 (1% solution in water); 5.02 (~1% w/v solution in water at room temperature)
Melting Point by DSC: 270°C followed by decomposition
Partition co-efficient: Log P =1.76 (n-octanol/buffer, pH 7.4 at 37°C; 1.6 (n-octanol/buffer, pH 6.97)
Composition
APO-NALTREXONE tablets contain 50 mg of naltrexone hydrochloride. Non- medicinal ingredients colloidal silicon dioxide, hydroxypropyl cellulose, hydroxypropyl methylcellulose, iron oxide red, iron oxide yellow, lactose monohydrate, magnesium stearate, polyethylene glycol and titanium dioxide.
Stability and Storage Recommendations
Store at controlled room temperature (15°C-30°C). Protect from moisture.
AVAILABILITY OF DOSAGE FORMS
APO-NALTREXONE tablets are available as 50 mg, pale yellow, oval, biconvex, film coated tablets. Engraved “NAL” score “50” on one side, “APO” on the other side. Available in bottles of 30 and 50 tablets.