


Product Monograph - Apo-Warfarin (Apotex, 1 mg, ..., 10 mg)
Recent Major Label Changes
| 7 Warnings and Precautions, Renal | 2026-01 |
|---|
Table of Contents
Certain sections or subsections that are not applicable at the time of the preparation of the most recent authorized product monograph are not listed.
Recent Major Label Changes .................................................................................................... 2
Table of Contents .................................................................................................................... 2
Part 1: Healthcare Professional Information ............................................................................ 4
- 1.
Indications ................................................................................................................... 4
1.1. Pediatrics ............................................................................................................... 4
1.2. Geriatrics ............................................................................................................... 4
- 2. Contraindications ......................................................................................................... 4
- 3. Serious Warnings and Precautions Box ........................................................................ 5
- 4.
Dosage and Administration .......................................................................................... 6
4.1. Dosing Considerations ........................................................................................... 6
4.2. Recommended Dose and Dosage Adjustment ...................................................... 8
4.4. Administration ....................................................................................................... 9
4.5. Missed Dose .......................................................................................................... 9
- 5. Overdose...................................................................................................................... 9
- 6. Dosage Forms, Strengths, Composition, and Packaging .............................................. 10
- 7.
Warnings and Precautions .......................................................................................... 10
General ............................................................................................................................ 10
Cardiovascular ................................................................................................................. 10
Endocrine and Metabolism ............................................................................................. 12
Hematologic .................................................................................................................... 12
Immune ........................................................................................................................... 13
Monitoring and Laboratory Tests .................................................................................... 13
Peri-Operative Considerations ........................................................................................ 14
Renal ............................................................................................................................... 14
Sensitivity/Resistance ...................................................................................................... 14
Skin .................................................................................................................................. 14
7.1. Special Populations .............................................................................................. 15
7.1.1. Pregnancy ........................................................................................................ 15
7.1.2. Breastfeeding .................................................................................................. 16
7.1.3. Pediatrics ......................................................................................................... 16
7.1.4. Geriatrics ......................................................................................................... 16
- 8.
Adverse Reactions ...................................................................................................... 17
8.1. Adverse Reaction Overview ................................................................................. 17
8.5. Post-Market Adverse Reactions .......................................................................... 17
- 9.
Drug Interactions ....................................................................................................... 18
9.2. Drug Interactions Overview ................................................................................. 18
9.4. Drug-Drug Interactions ........................................................................................ 19
9.5. Drug-Food Interactions ........................................................................................ 25
9.6. Drug-Herb Interactions ........................................................................................ 25
9.7. Drug-Laboratory Test Interactions ....................................................................... 27
- 10.
Clinical Pharmacology ................................................................................................ 27
10.1. Mechanism of Action ....................................................................................... 27
10.2. Pharmacodynamics ......................................................................................... 28
10.3. Pharmacokinetics ............................................................................................ 28
- 11. Storage, Stability, and Disposal .................................................................................. 30
- 12. Special Handling Instructions ..................................................................................... 30
Part 2: Scientific Information ................................................................................................. 31
- 13. Pharmaceutical Information ....................................................................................... 31
- 14.
Clinical Trials .............................................................................................................. 31
14.2. Comparative Bioavailability Studies ................................................................. 31
- 15. Microbiology .............................................................................................................. 34
- 16. Non-Clinical Toxicology .............................................................................................. 34
- 17. Supporting Product Monograph ................................................................................. 34
Patient Medication Information ............................................................................................ 35
Part 1: Healthcare Professional Information
1. Indications
APO-WARFARIN (warfarin sodium) is indicated:
For the prophylaxis and/or treatment of venous thrombosis and its extension, pulmonary embolism, atrial fibrillation with embolization, and as an adjunct in the prophylaxis of systemic embolism after myocardial infarction, including stroke and reinfarction.
The following are some of the more common clinical disorders which may be associated with or predispose patients to the above indications:
- 1. Thrombophlebitis
- 2. Congestive heart failure
- 3. Surgical procedure or trauma associated with a high risk of thromboembolism
- 4. Myocardial infarction
- 5. Cerebral embolism
- As an adjunct in the treatment of transient cerebral ischemic attacks due to intravascular clotting.
1.1. Pediatrics
Pediatrics (<18 years of age): Based on the data submitted and reviewed by Health Canada, the safety and efficacy of warfarin sodium in pediatric patients has not been established; therefore, Health Canada has not authorized an indication for pediatric use. See 7.1.3 Pediatrics.
1.2. Geriatrics
Geriatrics (≥ 60 years of age): Evidence from clinical studies and experience suggests that use in the geriatric population is associated with differences in safety or effectiveness. See 7.1.4 Geriatrics and 10.3 Pharmacokinetics, Special Populations and Conditions, Geriatrics.
2. Contraindications
APO-WARFARIN is contraindicated in:
- Patients who are hypersensitive to this drug or to any ingredient in the formulation, including any non-medicinal ingredient, or component of the container. For a complete listing, see 6 Dosage Forms, Strengths, Composition, and Packaging.
APO-WARFARIN is also contraindicated in patients with any localized or general physical condition or personal circumstances in which the hazard of haemorrhage might be greater than the potential clinical benefits of anticoagulation, such as:
Pregnancy
APO-WARFARIN (warfarin sodium) is contraindicated in pregnancy because the drug passes through the placental barrier and may cause fatal haemorrhage to the fetus in utero. Women of childbearing potential must take precautions not to become pregnant while on APO-WARFARIN therapy. Furthermore, there have been reports of birth malformations in
- children born to mothers who have been treated with warfarin during pregnancy. See 7.1.1 Pregnancy.
- Haemorrhagic tendencies or blood dyscrasias
Recent or contemplated surgery of:
- 1. central nervous system
- 2. eye
- 3. traumatic surgery resulting in large open surfaces
Bleeding tendencies associated with active ulceration or overt bleeding of:
- 1. gastrointestinal, genitourinary or respiratory tracts
- 2. central nervous system haemorrhage
- 3. cerebral aneurysms or dissecting aorta
- 4. pericarditis and pericardial effusions
- 5. bacterial endocarditis
- Threatened abortion, eclampsia and preeclampsia
- Inadequate laboratory facilities
- Unsupervised patients with conditions associated with potential high level of noncompliance such as senility, alcoholism, or psychosis or other lack of patient cooperation
- Spinal puncture and other diagnostic or therapeutic procedures with potential for uncontrollable bleeding
- Major regional or lumbar block anesthesia
- Malignant hypertension
- Serious Warnings and Precautions Box
Serious Warnings and Precautions
BLEEDING RISK: APO-WARFARIN can cause major or fatal bleeding. Bleeding is more likely to occur during the starting period and with a higher dose (resulting in a higher INR). Risk factors for bleeding include high intensity of anticoagulation (INR >4.0), age ≥65, highly variable INRs, history of gastrointestinal bleeding, hypertension, cerebrovascular disease, serious heart disease, anemia, malignancy, trauma, renal insufficiency, concomitant drugs (see 7 Warnings and Precautions, Hematologic and 9.4 Drug-Drug Interactions), and long duration of warfarin therapy. Regular monitoring of INR should be performed on all treated patients. Those at high risk of bleeding may benefit from more frequent INR monitoring, careful dose adjustment to desired INR, and a shorter duration of therapy appropriate for the clinical condition. However, maintenance of INR in the therapeutic range does not eliminate the risk of bleeding. Drugs, dietary changes, and other factors affect INR levels achieved with APO-WARFARIN therapy. Perform more frequent INR monitoring when starting or stopping other drugs, including botanicals, or when changing dosages of other drugs. Patients should be instructed about prevention measures to minimize risk of bleeding and to report immediately to physicians signs and symptoms of bleeding. See 7 Warnings and Precautions, Monitoring and Laboratory Tests. An INR of greater than 4.0 appears to provide no additional therapeutic benefit in most patients and is associated with a higher risk of pathological bleeding.
4. Dosage and Administration
4.1. Dosing Considerations
The administration and dosage of APO-WARFARIN (warfarin sodium) must be individualized according to the patient’s responsiveness to the drug. The dosage should be adjusted according to results of the patient’s PT ratio/INR. Measurement of warfarin induced effects on PT can vary substantially due to the sensitivity of different thromboplastin reagents.
Early clinical studies of oral anticoagulants, which formed the basis for recommended therapeutic ranges of 1.5 to 2.5 times control PT, used sensitive human brain thromboplastin. When using the less sensitive rabbit brain thromboplastins commonly employed in PT assays today, adjustments must be made to the targeted PT range that reflect this decrease in sensitivity.
The best available information supports the following recommendations for dosing of APO-WARFARIN.
Venous Thromboembolism (including deep venous thrombosis [DVT] and pulmonary embolism [PE])
For patients with a first episode of DVT or PE secondary to a transient (reversible) risk factor, treatment with warfarin for 3 months is generally recommended. For patients with a first episode of idiopathic DVT or PE, warfarin is generally recommended for at least 6 to 12 months. For patients with two or more episodes of documented DVT or PE, indefinite treatment with warfarin is suggested. For patients with specific risk factors (e.g. documented antiphospholipid antibodies), please refer to current treatment guidelines for recommended duration of treatment.
The dose of warfarin should be adjusted to maintain a target INR of 2.5 (INR range, 2.0 to 3.0) for all treatment durations.
Atrial Fibrillation
Five recent clinical trials evaluated the effects of warfarin in patients with non-valvular atrial fibrillation (AF). Findings of these studies revealed that the effects of warfarin in reducing thromboembolic events including stroke were similar at either moderately high INR (2.0 to 4.5) or low INR (1.4 to 3.0). There was a significant reduction in minor bleeds at the low INR. There are no adequate and well-controlled studies in populations with atrial fibrillation and valvular heart disease. Although clinical studies have used a wide range of warfarin dosing, a more recent study suggests that in patients with atrial fibrillation, anticoagulant prophylaxis is effective at INRs of 2.0 to 3.0. The study also shows that the risk of thromboembolic stroke may increase substantially at INR's less than 2.0. INR value should not exceed 4.0, to reduce the risk of anticoagulant-related bleeding.
Similar data from clinical studies in valvular atrial fibrillation patients are not available. The trials in non-valvular atrial fibrillation support the recommendation that an INR of 2.0 to 3.0 be used for long term warfarin therapy in appropriate AF patients. In cases where the risk of thromboembolism is great, such as in patients with recurrent systemic embolism, a higher INR may be required. An INR ratio of greater than 4.0 appears to provide no additional therapeutic benefit in most patients and is associated with a higher risk of bleeding. In AF patients undergoing elective cardioversion, anticoagulant therapy should be given for three weeks before cardioversion and continued until normal sinus rhythm has been maintained for four weeks.
Oral anticoagulation is recommended in patients with persistent or paroxysmal atrial fibrillation without valvular disease but at high risk of embolic stroke, i.e., having any of the following features: prior ischemic stroke, transient ischemic attack, or systemic embolism; age >75 years; moderately or severely impaired left ventricular systolic function or congestive heart failure, history of hypertension, or diabetes mellitus. For patients at lower risk, individualized treatment is required. For patients with atrial fibrillation and valvular heart disease, especially mitral valve stenosis, anticoagulation is recommended. For patients with atrial fibrillation and prosthetic heart valves, anticoagulation is required, with the target INR generally increased, with or without aspirin added, depending of risk factors related to the replaced valve or inherent to the patient.
Post-Myocardial Infarction
For most patients following myocardial infarction and not at high risk, antithrombotic treatment should consist of aspirin alone. In patients with acute coronary syndrome that were revascularised by percutaneous coronary intervention (PCI), clopidogrel is usually added. For high-risk patients with myocardial infarction (MI), including those with a large anterior MI, significant heart failure, intracardiac thrombus visible on echocardiography, or those with a history of a thromboembolic event, therapy with combined moderate-intensity warfarin (INR 2.0 to 3.0) plus low-dose aspirin (100 mg/day) for 3 months following myocardial infarction should be considered.
Renal Impairment
While no dosage adjustment is necessary for patients with renal failure, frequent monitoring of anticoagulation is advised in patients with compromised renal function to maintain warfarin dosage within the therapeutic range. See 7 Warnings and Precautions, Renal, Use in Patients with altered glomerular integrity.
Laboratory Control
The Prothrombin Time (PT) should be determined daily after the administration of the initial dose until International Normalized Ratio (INR) results stabilize in the therapeutic range. Intervals between subsequent INR determinations should be based upon the physician's judgment of the patient's reliability and response to warfarin in order to maintain the individual within the therapeutic range. Acceptable intervals for INR determinations are normally within the range of one to four weeks after a stable dosage has been determined.
To ensure adequate control, it is recommended that additional PT tests be done when other warfarin products are interchanged with warfarin sodium tablets, as well as whenever other medications are initiated, discontinued, or taken irregularly (see 7 Warnings and Precautions, Monitoring and Laboratory Tests). Safety and efficacy of warfarin therapy can be improved by increasing the quality of laboratory control. Reports suggest that in usual care monitoring, patients are in therapeutic range only 33% to 64% of the time. Time in therapeutic range is significantly greater (56% to 93%) in patients managed by anticoagulation clinics.
In switching to another warfarin product, particular emphasis needs to be placed on INR control. INR outside of the therapeutic range may result in serious clinical consequences: lack of efficacy leading to thromboembolic stroke or myocardial infarction, if INR values are low, and intracranial bleeding if they are high.
4.2. Recommended Dose and Dosage Adjustment
Initial Dosage
The dosing of APO-WARFARIN must be individualized according to the patient’s sensitivity to the drug as indicated by the PT/INR. Use of a large loading dose may increase the incidence of hemorrhagic and other complications, does not offer more rapid protection against thrombi formation, and is not recommended. It is recommended that APO-WARFARIN therapy be initiated with a dose of 2 to 5 mg per day with dosage adjustments based on the results of PT/INR determinations. The lower initiation doses should be considered for patients with certain genetic variations in CYP2C9 and VKORC1 enzymes as well as for elderly and/or debilitated patients and patients with potential to exhibit greater than expected PT/INR responses to warfarin. Elderly and Asian patients may require lower initiation and maintenance doses of warfarin sodium. See 9 Drug Interactions.
Maintenance
Most patients are satisfactorily maintained at a dose of 2 to 10 mg daily. Flexibility of dosage is provided by breaking scored tablets in half. The individual dose and interval should be gauged by the patient’s prothrombin response.
Duration of Therapy
The duration of therapy in each patient should be individualized. In general, anticoagulant therapy should be continued until the danger of thrombosis and embolism has passed.
TREATMENT DURING DENTISTRY AND SURGERY
The management of patients who undergo dental and surgical procedures requires close liaison between attending physicians, surgeons and dentists. PT ratio/INR determination is recommended just prior to any dental or surgical procedure. In patients undergoing minimal invasive procedures who must be anticoagulated prior to, during, or immediately following these procedures, adjusting the dosage of APO-WARFARIN to maintain the PT ratio/INR at the low end of the therapeutic range, may safely allow for continued anticoagulation. The operative site should be sufficiently limited and accessible to permit the effective use of local procedures for haemostasis.
Under these conditions, dental and surgical procedures may be performed without undue risk of haemorrhage. Some dental or surgical procedures may necessitate the interruption of APO-WARFARIN therapy. When discontinuing APO-WARFARIN even for a short period of time, the benefits and risks should be strongly considered.
CONVERSION FROM HEPARIN THERAPY
Since the anticoagulant effect of warfarin sodium is delayed, heparin is preferred initially for rapid anticoagulation. Conversion to APO-WARFARIN may begin concomitantly with heparin therapy or may be delayed 3 to 6 days. To ensure continuous anticoagulation, it is advisable to continue full dose heparin therapy and that APO-WARFARIN therapy be overlapped with heparin for 4 to 5 days, until APO-WARFARIN has produced the desired therapeutic response as determined by PT ratio/INR. When APO-WARFARIN has produced the desired PT ratio/INR or prothrombin activity, heparin may be discontinued.
APO-WARFARIN may increase the aPTT test, even in the absence of heparin. During initial therapy with APO-WARFARIN, the interference with heparin anticoagulation is of minimal clinical significance.
As heparin may affect the PT, patients receiving both heparin and APO-WARFARIN should have blood drawn for PT ratio/INR determination, at least:
- 5 hours after the last IV bolus dose of heparin, or
- 4 hours after cessation of a continuous IV infusion of heparin, or
- 24 hours after last subcutaneous heparin injection.
4.4. Administration
APO-WARFARIN tablets should be taken orally either with food or on an empty stomach.
4.5. Missed Dose
The anticoagulant effect of warfarin sodium persists beyond 24 hours. If the patient forgets to take the prescribed dose of APO-WARFARIN at the scheduled time, the dose should be taken as soon as possible on the same day. The patient should not take the missed dose by doubling the daily dose to make up for missed doses, but should refer back to his or her physician.
5. Overdose
Signs and Symptoms:
Suspected or overt abnormal bleeding (e.g., appearance of blood in stools or urine, haematuria, excessive menstrual bleeding, melena, petechiae, excessive bruising or persistent oozing from superficial injuries, unexplained fall in hemoglobin) is a manifestation of excessive anticoagulation.
Treatment
The treatment of excessive anticoagulation is based on the level of the INR, the presence or absence of bleeding, and clinical circumstances. Excessive anticoagulation may be controlled by discontinuing APO-WARFARIN (warfarin sodium) therapy and if necessary, by administration of oral or parenteral vitamin K1. (Please see recommendations accompanying vitamin K1 preparations prior to use.)
Such use of vitamin K1 reduces responses to subsequent warfarin sodium therapy. Patients may return to a pretreatment thrombotic status following the rapid reversal of a prolonged INR.
Resumption of warfarin administration reverses the effect of vitamin K1, and a therapeutic INR can again be obtained by careful dosage adjustment. If rapid anticoagulation is indicated, heparin may be preferable for initial therapy.
If minor bleeding progresses to major bleeding, give 5 to 25 mg (rarely up to 50 mg) parenteral vitamin K1. Prothrombin complex concentrate (PCC), fresh frozen plasma, or activated Factor VII treatment may be considered if the requirement to reverse the effects of APO-WARFARIN is urgent.
A risk of hepatitis and other viral diseases is associated with the use of these blood products; PCC and activated Factor VII are also associated with an increased risk of thrombosis. Therefore, these preparations should be used only in exceptional or life-threatening bleeding episodes secondary to APO-WARFARIN overdosage.
Purified Factor IX preparations should not be used because they cannot increase the levels of prothrombin, Factor VII and Factor X, which are also depressed along with the levels of Factor IX as a result of APO-WARFARIN treatment. Packed red blood cells may also be given if significant blood loss has occurred. Infusions of blood or plasma should be monitored carefully to avoid precipitating pulmonary edema in elderly patients or patients with heart disease.
For the most recent information in the management of a suspected drug overdose, contact your regional poison control centre or Health Canada’s toll-free number, 1-844 POISON-X (1-844-764-7669).
- 6. Dosage Forms, Strengths, Composition, and Packaging
Table 1 – Dosage Forms, Strengths, and Composition
Description
1 mg: each round, pink, biconvex, scored tablet engraved “WAR” over “1” on one side and “APO” on the other contains 1 mg warfarin sodium. Available in bottles of 100 and 500.
2 mg: each round, lavender, biconvex, scored tablet engraved “WAR” over “2” on one side and “APO” on the other contains 2 mg warfarin sodium. Available in bottles of 100 and 500.
2.5 mg: each round, green, biconvex, scored tablet engraved “WAR” over “2.5” on one side and “APO” on the other contains 2.5 mg warfarin sodium. Available in bottles of 100 and 500.
4 mg: each round, blue, biconvex, scored tablet engraved “WAR” over “4” on one side and “APO” on the other contains 4 mg warfarin sodium. Available in bottles of 100 and 500.
5 mg: each round, peach, biconvex, scored tablet engraved “WAR” over “5” on one side and “APO” on the other contains 5 mg warfarin sodium. Available in bottles of 100 and 500.
10 mg: each round, white, biconvex, scored tablet engraved “WAR” over “10” on one side and “APO” on the other contains 10 mg warfarin sodium. Available in bottles of 100.
7. Warnings and Precautions
General
Concomitant use of anticoagulants with streptokinase or urokinase is not recommended and may be hazardous. (Please note recommendations accompanying these preparations).
Cardiovascular
Patients with congestive heart failure may become more responsive to APO-WARFARIN, thereby
| Route of Administration | Dosage Form / Strength/Composition | Non-medicinal Ingredients |
| Oral | Tablet 1 mg, 2 mg, 2.5 mg, 4 mg, 5 mg, 10 mg of warfarin sodium. | Corn starch, lactose monohydrate, magnesium stearate, microcrystalline cellulose and colour dyes which vary in each tablet strength. 1 mg: D&C Red No. 30 and FD&C Yellow No. 6 2 mg: D&C Red No. 7 and ferric-ferrous oxide 2.5 mg: FD&C Blue No. 1 and D&C Yellow No. 10 4 mg: FD&C Blue No. 1 5 mg: FD&C Yellow No. 6 and D&C Yellow No. 10 10 mg: Dye free |
requiring more frequent laboratory monitoring, and reduced doses of APO-WARFARIN.
Systemic atheroemboli and cholesterol microemboli
Anticoagulation therapy with APO-WARFARIN may enhance the release of atheromatous plaque emboli, thereby increasing the risk of complications from systemic cholesterol microembolization, including the "purple toe syndrome". While the "purple toe syndrome" is reported to be reversible, other complications of microembolization may not be reversible.
Systemic atheroemboli and cholesterol microemboli can present with a variety of signs and symptoms including purple toe syndrome, livedo reticularis, rash, gangrene, abrupt and intense pain in the leg, foot, or toes, foot ulcers, myalgia, penile gangrene, abdominal pain, flank or back pain, hematuria, renal insufficiency, hypertension, cerebral ischemia, spinal cord infarction, pancreatitis, symptoms simulating polyarteritis, or any other sequelae of vascular compromise due to embolic occlusion. The most commonly involved visceral organs are the kidneys followed by the pancreas, spleen, and liver. Some cases have progressed to necrosis or death. Discontinue APO-WARFARIN therapy if such phenomena are observed. Consider alternative drugs if continued anticoagulation therapy is necessary.
Purple toe syndrome is a complication of oral anticoagulation characterized by a dark, purplish or mottled color of the toe, usually occurring between 3 to 10 weeks, or later, after the initiation of therapy with warfarin or related compounds. Major features of this syndrome include purple color of plantar surfaces and sides of the toes that blanches on moderate pressure and fades with elevation of the legs; pain and tenderness of the toes, waxing and waning of the color over time. While the purple toes syndrome is reported to be reversible, some cases progress to gangrene or necrosis which may require debridement of the affected area, or may lead to amputation.
A severe elevation (>50 seconds) in activated partial thromboplastin time (aPTT) with a PT ratio/INR in the desired range has been identified as an indication of increased risk of postoperative haemorrhage. This has been noted in patients undergoing elective hip surgery receiving warfarin alone.
Administration of anticoagulants in the following conditions will be based upon clinical judgement in which the risks of anticoagulant therapy are weighed against the risk of thrombosis or embolization in untreated cases. The following may be associated with these increased risks:
- 1. Severe to moderate hepatic impairment or renal insufficiency.
- 2. Infectious diseases or disturbances of intestinal flora, such as sprue or as seen with antibiotic use.
- 3. Trauma which may result in internal bleeding.
- 4. Surgery or trauma resulting in large exposed raw surfaces.
- 5. Indwelling catheters.
- 6. Severe to moderate hypertension.
- 7. Deficiency in protein C–mediated anticoagulant response: APO-WARFARIN reduces the synthesis of the naturally occurring anticoagulants, protein C and protein S. Hereditary or acquired deficiencies of protein C or its cofactor, protein S, have been associated with tissue necrosis following warfarin administration. Not all patients with these conditions develop necrosis, and tissue necrosis occurs in patients without these deficiencies. Inherited resistance to activated protein C has been described in many patients with venous thromboembolic disorders but has not yet been evaluated as a risk factor for tissue necrosis. The risk associated with these conditions, both for recurrent thrombosis and for adverse reactions, is difficult to evaluate since it does not appear to be the same for everyone. Decisions about testing and therapy must be made on an individual basis. It has been reported that concomitant anticoagulation therapy with heparin for 5 to 7 days during initiation of therapy with warfarin may minimize the incidence of tissue necrosis. Warfarin therapy should be discontinued when warfarin is suspected to be the cause of developing necrosis and heparin therapy may be considered for anticoagulation.
- 8. Eye surgery: In cataract surgery, APO-WARFARIN use was associated with a significant increase in minor complications of sharp needle and local anesthesia block, but not associated with potentially sight-threatening operative hemorrhagic complications. As APO-WARFARIN cessation or reduction may lead to serious thromboembolic complications, the decision to discontinue APO-WARFARIN before a relatively less invasive and complex eye surgery, such as lens surgery, should be based upon the risks of anticoagulant therapy weighed against the benefits.
- 9. Diseases affecting the microvasculature or microcirculation, such as polycythemia vera, vasculitis, and severe diabetes.
- 10. Poor nutritional state.
- 11. Vitamin K deficiency.
- 12. Increased vitamin K intake.
- 13. Hereditary warfarin resistance.
Endocrine and Metabolism
Calciphylaxis
Calciphylaxis, also known as calcific uremic arteriolopathy, has been reported in predisposed patients, mainly end-stage renal disease (ESRD) patients under dialysis, but also patients with known risk factors such as hyperphosphatemia, hypercalcemia, low serum albumin levels or receiving vitamin K antagonists, including warfarin. When calciphylaxis is diagnosed in these patients, discontinue APO-WARFARIN, start specific calciphylaxis supportive treatments, and consider if continued alternative anticoagulation therapy is necessary.
Hematologic
Haemorrhage
The most serious risk associated with anticoagulant therapy with warfarin sodium is haemorrhage in any tissue or organ (see 3 Serious Warnings and Precautions Box). The risk of haemorrhage is related to the level of intensity and the duration of anticoagulant therapy. Haemorrhage has in some cases been reported to result in death or permanent disability.
It cannot be emphasized too strongly that treatment of each patient is a highly individualized matter. APO-WARFARIN, a narrow therapeutic range (index) drug, may be affected by factors such as other drugs and dietary Vitamin K. Dosage should be controlled by periodic determinations of prothrombin times (PT) ratio/ International Normalized Ratio (INR) or other suitable coagulation tests. Determinations of whole blood clotting and bleeding times are not effective measures for control of therapy. Heparin prolongs the one-stage PT. When heparin and warfarin sodium are administered concomitantly, refer above to CONVERSION FROM HEPARIN THERAPY for recommendations.
Drugs, dietary changes, and other factors affect INR levels achieved with APO-WARFARIN therapy. Perform more frequent INR monitoring when starting or stopping other drugs, including botanicals, or when changing dosages of other drugs. See 9 Drug Interactions.
Caution should be observed when APO-WARFARIN is administered in any situation or in the presence of any predisposing condition where added risk of haemorrhage, necrosis and/or gangrene is present.
Heparin-Induced Thrombocytopenia
Do not use APO-WARFARIN as initial therapy in patients with heparin-induced thrombocytopenia (HIT) and with heparin-induced thrombocytopenia with thrombosis syndrome (HITTS). Cases of limb ischemia, necrosis, and gangrene have occurred in patients with HIT and HITTS when heparin treatment was discontinued and warfarin therapy was started or continued especially when large initiation doses were used. In some patients sequelae have included amputation of the involved area and/or death. The use of alternative anticoagulant therapy should be considered in patients with heparin-induced thrombocytopenia and deep vein thrombosis. Treatment with APO-WARFARIN may be considered after the platelet count has normalized.
Considerations for Increased Bleeding Risk
Warfarin sodium is a narrow therapeutic range (index) drug, and additional caution should be observed when warfarin sodium is administered to certain patients. Reported risk factors for bleeding include high intensity of anticoagulation (INR >4.0), age ≥65, highly variable INRs, history of gastrointestinal bleeding, hypertension, cerebrovascular disease, serious heart disease, anemia, malignancy, trauma, renal insufficiency, concomitant drugs (see 9.4 Drug-Drug Interactions) and long duration of warfarin therapy. Identification of risk factors for bleeding and certain genetic variations in CYP2CP and VKORC1 in a patient may increase the need for more frequent INR monitoring and the use of lower warfarin doses (see 10.3 Pharmacokinetics, Metabolism and 4 Dosage and Administration). Bleeding is more likely to occur during the starting period and with a higher dose of warfarin sodium (resulting in a higher INR).
Intramuscular (I.M.) injections of concomitant medications should be confined to the upper extremities which permit easy access for manual compression, inspections for bleeding and use of pressure bandages.
Caution should be observed when APO-WARFARIN (or warfarin) is administered concomitantly with nonsteroidal anti-inflammatory drugs (NSAIDs), including aspirin, to be certain that no change in anticoagulation dosage is required. In addition to specific drug interactions that might affect PT/INR, NSAIDs, including aspirin, can inhibit platelet aggregation, and can cause gastrointestinal bleeding, peptic ulceration and/or perforation.
Immune
Minor and severe allergic/hypersensitivity reactions and anaphylactic reactions have been reported.
Monitoring and Laboratory Tests
Periodic determination of PT ratio/INR or other suitable coagulation test is essential. See 4.1 Dosing Considerations, Laboratory Control.
Numerous factors, alone or in combination, including travel, changes in diet, environment, physical state or medication, or the use of natural medicines, may influence the patient’s response to anticoagulants including warfarin. It is generally good practice to monitor the patient’s response with additional PT ratio/INR determinations in the period immediately after discharge from the hospital, and whenever other medications, including natural medicines, are initiated, discontinued or taken irregularly. This includes drugs intended for short-term use (eg, antibiotics, antifungals, corticosteroids). The tables in the section 9.4 Drug-Drug Interactions provide a listing of factors, alone or in combination, which may affect the PT. However, other factors may also affect the anticoagulant response and the tables are provided for your reference only.
Drugs may interact with APO-WARFARIN (warfarin sodium) through pharmacodynamic or pharmacokinetic mechanisms. Pharmacodynamic mechanisms for drug interactions with APO-WARFARIN are synergism (impaired hemostasis, reduced clotting factor synthesis), competitive antagonism (vitamin K), and altered physiologic control loop for vitamin K metabolism (hereditary resistance). Pharmacokinetic mechanisms for drug interactions with APO-WARFARIN are mainly enzyme induction, enzyme inhibition, and reduced plasma protein binding. It is important to note that some drugs may interact by more than one mechanism.
Because a patient may be exposed to a combination of listed factors, the net effect of APO-WARFARIN on PT ratio/lNR responses may be unpredictable. More frequent PT/INR monitoring should be performed when starting or stopping other drugs, including botanicals, or when changing dosages of other drugs, including drugs intended for short-term use (eg, antibiotics, antifungals, corticosteroids). Consult the labeling of all concurrently used drugs to obtain further information about interactions with APO-WARFARIN or adverse reactions pertaining to bleeding. Intramuscular injections of concomitant medications should be confined to the upper extremities which permit easy access for manual compression, inspections for bleeding and use of pressure bandages.
Peri-Operative Considerations
Treatment during dentistry and surgery
Some dental or surgical procedures may necessitate the interruption or change in the dose of APO-WARFARIN therapy. Consider the benefits and risks when discontinuing APO-WARFARIN even for a short period of time. Determine the INR immediately prior to any dental or surgical procedure. In patients undergoing minimally invasive procedures who must be anticoagulated prior to, during, or immediately following these procedures, adjusting the dosage of APO-WARFARIN to maintain the INR at the low end of the therapeutic range may safely allow for continued anticoagulation.
Renal
Renal impairment
Patients with renal impairment who are taking warfarin should be instructed to be more vigilant in monitoring their INR.
Use in Patients with altered glomerular integrity
In patients with altered glomerular integrity or with a history of kidney disease, acute kidney injury may occur, possibly in relation to episodes of excessive anticoagulation and hematuria. See 4.1 Dosing Considerations, Renal Impairment.
Anticoagulant-related nephropathy
There have been post-marketing reports of anticoagulant-related nephropathy (ARN) following warfarin use, presenting as acute kidney injury. Close monitoring including renal function evaluation is advised in patients with a supratherapeutic INR, and hematuria.
Sensitivity/Resistance
In patients with acquired or inherited warfarin resistance, decreased therapeutic responses to warfarin have been reported. Exaggerated therapeutic responses have been reported in other patients.
Skin
Tissue Necrosis
Necrosis and/or gangrene of skin and other tissues is an uncommon but serious risk (<0.1%). It may be associated with local thrombosis and usually appears within a few days of the start of APO-WARFARIN therapy. In severe cases of necrosis, treatment through debridement or amputation of the affected tissue, limb, breast, or penis has been reported. Necrosis has in some cases been reported to result in death or permanent disability.
Careful clinical evaluation is required to determine whether necrosis is caused by an underlying disease. Warfarin therapy should be discontinued when warfarin is suspected to be the cause of developing necrosis and heparin therapy may be considered for anticoagulation. Although various treatments have been attempted, no treatment for necrosis has been considered uniformly effective. See below for information on predisposing conditions. These and other risks associated with anticoagulant therapy must be weighed against the risk of thrombosis or embolization in untreated cases. Discontinue APO-WARFARIN therapy if necrosis occurs. Consider alternative drugs if continued anticoagulation therapy is necessary.
7.1. Special Populations
7.1.1. Pregnancy
APO-WARFARIN (warfarin sodium) is contraindicated in pregnancy. In humans, warfarin crosses the placenta, and concentrations in fetal plasma approach the maternal values and may cause fatal haemorrhage to the fetus in utero. Women of childbearing potential must take precautions not to become pregnant while on APO-WARFARIN therapy. Furthermore, there have been reports of birth malformations in children born to mothers who have been treated with warfarin during pregnancy.
Exposure to warfarin during the first trimester of pregnancy caused a pattern of congenital malformations in about 5% of exposed offspring. Warfarin embryopathy is characterized by nasal hypoplasia with or without stippled epiphyses (chondrodysplasia punctata) and growth retardation (including low birth weight). Central nervous system and eye abnormalities have also been reported, including dorsal midline dysplasia characterized by agenesis of the corpus callosum, Dandy-Walker malformation, midline cerebellar atrophy, and ventral midline dysplasia characterized by optic atrophy. Mental retardation, blindness, schizencephaly, microcephaly, hydrocephalus, and other adverse pregnancy outcomes have been reported following warfarin exposure during the second and third trimesters of pregnancy. Although rare, teratogenic reports following in utero exposure to warfarin also include urinary tract anomalies such as single kidney, asplenia, anencephaly, spina bifida, cranial nerve palsy, cardiac defects and congenital heart disease, polydactyly, deformities of toes, diaphragmatic hernia, corneal leukoma, cleft palate and cleft lip. See 2 Contraindications.
Spontaneous abortion and still birth are known to occur and a higher risk of fetal mortality is associated with the use of warfarin. Low birth weight and growth retardation have also been reported.
APO-WARFARIN exposure during pregnancy can cause pregnancy loss, birth defects, or fetal death. Women of childbearing potential who are candidates for anticoagulant therapy should be carefully evaluated and the indications critically reviewed with the patient. Discuss pregnancy planning with females of reproductive potential who are on APO-WARFARIN therapy. If the patient becomes pregnant while taking this drug, she should be apprised of the potential risks to the fetus, and the possibility of termination of the pregnancy should be discussed in the light of those risks. See 2 Contraindications, Pregnancy.
7.1.2. Breastfeeding
Based on published data in 15 nursing mothers, warfarin was not detected in human milk. Among the 15 full-term newborns, 6 nursing infants had documented prothrombin times within the expected range. Prothrombin times were not obtained for the other 9 nursing infants. Monitor breastfeeding infants for bruising or bleeding. Effects in premature infants have not been evaluated. Caution should be exercised when APO-WARFARIN is administered to a nursing woman. The decision to breast-feed should be undertaken only after careful consideration of the available alternatives. Women who are breast-feeding and anticoagulated with warfarin should be very carefully monitored so that recommended INR values are not exceeded. It is prudent to perform coagulation tests on infants at risk for bleeding before advising women taking warfarin to breast-feed.
7.1.3. Pediatrics
Pediatrics (<18 years of age): Safety and effectiveness in children below 18 years of age have not been established in randomized, controlled clinical trials. However, the use of warfarin sodium in pediatric patients has been documented for the prevention and treatment of thromboembolic events.
Adequate and well-controlled studies with warfarin sodium have not been conducted in any pediatric population, and the optimum dosing, safety, and efficacy in pediatric patients is unknown. Pediatric use of warfarin sodium is based on adult data and recommendations, and available limited pediatric data from observational studies and patient registries. Pediatric patients administered APO-WARFARIN should avoid any activity or sport that may result in traumatic injury.
The developing hemostatic system in infants and children results in a changing physiology of thrombosis and response to anticoagulants. Dosing of warfarin in the pediatric population varies by patient age, with infants generally having the highest, and adolescents having the lowest milligram per kilogram dose requirements to maintain target INRs. Because of changing warfarin requirements due to age, concomitant medications, diet, and existing medical condition, target INR ranges may be difficult to achieve and maintain in pediatric patients, and more frequent INR determinations are recommended. Bleeding rates varied by patient population and clinical care center in pediatric observational studies and patient registries.
Infants and children receiving vitamin K–supplemented nutrition, including infant formulas, may be resistant to warfarin therapy, while human-milk–fed infants may be sensitive to warfarin therapy.
7.1.4. Geriatrics
Geriatrics (≥ 60 years of age): Patients 60 years or older appear to exhibit greater than expected PT/INR response to the anticoagulant effects of warfarin (see 10.3 Pharmacokinetics, Special Populations and Conditions, Geriatrics). Warfarin sodium is contraindicated in any unsupervised patients with conditions associated with potential high level of noncompliance such as senility, alcoholism, or psychosis or other lack of patient cooperation. Caution should be exercised with administration of warfarin sodium to elderly and/or debilitated patients in any situation or physical condition where added risk of hemorrhage is present. Low initiation and maintenance doses of APO-WARFARIN are recommended in the elderly. See 4.2 Recommended Dose and Dosage Adjustment.
8. Adverse Reactions
8.1. Adverse Reaction Overview
Potential adverse reactions to APO-WARFARIN (warfarin sodium) may include:
Hemorrhage
Hemorrhage, ranging from minor to severe bleeding (including fatal outcomes), can occur during therapy with APO-WARFARIN. Hemorrhage may occur in any tissue or organ, manifesting as external or internal bleeding with associated symptoms and complications. This is a consequence of the anticoagulant effect.
Typically, the following body systems may be affected:
- upper (gingival bleeding, hematemesis) or lower (melena, hematochezia, rectal bleeding) gastrointestinal tract
- retroperitoneal space
- respiratory tract (epistaxis, hemoptysis), including rare cases of pulmonary alveolar hemorrhage
- genitourinary tract (hematuria, vaginal bleeding, menorrhagia)
- skin (contusion, ecchymosis, and petechia)
Central nervous system hemorrhage, including intracranial hemorrhage or spinal hematoma, ocular, intra-articular, pleural, pericardial, adrenal, and hepatic hemorrhage may also occur.
Some hemorrhagic complications may present as signs and symptoms that are not immediately identified as resulting from hemorrhage.
The signs, and symptoms, and severity will vary according to the location and degree or extent of the bleeding. Haemorrhagic complications may present as paralysis, paresthesia, headache, chest, abdomen, joint, muscle or other pain, dizziness, shortness of breath, difficult breathing or swallowing, unexplained swelling, weakness, hypotension, anaemia, purple toe syndrome, fatigue, lethargy, malaise, pallor, syncope or unexplained shock. Therefore, the possibility of haemorrhage should be considered in evaluating the condition of any anticoagulated patient with complaints which do not indicate an obvious diagnosis. Bleeding during anticoagulant therapy does not always correlate with PT ratio/INR. See 5 Overdose.
Bleeding which occurs when the PT ratio/INR is within the therapeutic range warrants diagnostic investigation, since it may unmask a previously unsuspected lesion, e.g. tumour, ulcer, etc.
Necrosis of skin and other tissues (see 7 Warnings and Precautions, Skin, Tissue Necrosis).
Systemic atheroemboli and cholesterol microemboli (see 7 Warnings and Precautions, Cardiovascular, Systemic atheroemboli and cholesterol microemboli)
8.5. Post-Market Adverse Reactions
The following adverse reactions have been reported from post-marketing experience with warfarin. Because these reactions are reported voluntarily from a population of uncertain size, it is not always possible to reliably estimate their frequency.
Blood and lymphatic system disorders: anemia.
Cases of atraumatic splenic rupture in patients taking warfarin have been reported.
Cardiac disorders: angina, chest pain, pericardial haemorrhage.
Endocrine disorders: adrenal haemorrhage.
Eye disorders: eye haemorrhage.
Gastrointestinal disorders: abdominal pain including cramping, abdominal distention, diarrhea, dysgeusia, dysphagia, flatulence/bloating, gingival bleeding, haematemesis, haematochezia, maelena, nausea, rectal haemorrhage, retroperitoneal haemorrhage, taste perversion, vomiting.
General disorders and administration site conditions: asthenia, fatigue, edema, swelling, feeling cold and chills, malaise, pain pallor, fever.
Hepatobiliary disorders: hepatitis, hepatic haemorrhage, jaundice, cholestatic hepatic injury.
Immune system disorders: anaphylactic reaction, hypersensitivity/allergic reactions.
Investigations: hepatic enzyme increased.
Metabolism and nutrition disorders: calciphylaxis.
Musculoskeletal, connective tissue and bone disorders: arthralgia, haemarthrosis, myalgia.
Nervous system disorders: dizziness, headache, haemorrhage intracranial, paraesthesia, paralysis, spinal haematoma, cold intolerance, coma, loss of consciousness.
Psychiatric disorders: lethargy.
Renal and urinary disorders: anticoagulant-related nephropathy (ARN), haematuria, acute kidney injury.
Reproductive system and breast disorders: vaginal haemorrhage, menorrhagia.
Priapism has been associated with anticoagulant administration; however, a causal relationship has not been established.
Respiratory, thoracic and mediastinal disorders: epistaxis, dyspnoea, haemoptysis, haemothorax, pulmonary alveolar haemorrhage, pulmonary calcification.
Rare events of tracheal or tracheobronchial calcification have been reported in association with long-term warfarin therapy. The clinical significance of this event is unknown.
Skin and subcutaneous tissue disorders: ecchymosis, pruritus, rash, alopecia, dermatitis, petechia, urticaria, skin necrosis, dermatitis bullous.
Vascular disorders: haemorrhage, hypotension, syncope, vasculitis, shock, blue toe syndrome, embolism arterial, fat embolism, necrosis, systemic cholesterol microembolization.
9. Drug Interactions
9.2. Drug Interactions Overview
CYP450 isozymes involved in the metabolism of warfarin include CYP2C9, 2C19, 2C8, 2C18, 1A2, and 3A4. The more potent warfarin S-enantiomer (60% of the overall anticoagulation response) is metabolized by CYP2C9 while the R-enantiomer is metabolized by CYP1A2 and 3A4. The steady state concentration of warfarin is mediated by CYP2C9 mediated metabolism of S-enantiomer).
- Inhibitors of CYP2C9, 1A2, and/or 3A4 have the potential to increase the effect (increase INR) of warfarin by increasing the exposure of warfarin.
Inducers of CYP2C9, 1A2, and/or 3A4 have the potential to decrease the effect (decrease
- INR) of warfarin by decreasing the exposure of warfarin.
Acquired or inherited warfarin resistance should be suspected if large daily doses of APO-WARFARIN are required to maintain a patient's PT ratio/INR within a normal therapeutic range.
Medications of unknown interaction with coumarins are best regarded with caution. When these medications are started or stopped, more frequent PT ratio/INR monitoring is advisable. Coumarins may also affect the action of other drugs. Hypoglycemic agents (chlorpropamide and tolbutamide) and anticonvulsants (phenytoin and phenobarbital) may accumulate in the body as a result of interference with either their metabolism or excretion.
It has been reported that concomitant administration of warfarin and ticlopidine may be associated with cholestatic hepatitis.
9.4. Drug-Drug Interactions
The drugs listed in this table are based on either drug interaction case reports or studies, or potential interactions due to the expected magnitude and seriousness of the interaction (i.e., those identified as contraindicated).
Table 2 - Established or Potential Drug-Drug Interactions
| Non-proprietary names of the drug products | Source of Evidence | Effect | Clinical comment |
| Non-proprietary names of the drug products | Source of Evidence | Effect | Clinical comment |
| Antibiotics and antifungals | CT | May change international normalized ratio (INR). | There have been reports of changes in INR in patients taking warfarin and antibiotics or antifungals, but clinical pharmacokinetic studies have not shown consistent effects of these agents on plasma concentrations of warfarin. Coadministration with warfarin should be avoided or closely monitor INR when starting or stopping any antibiotic or antifungal in patients taking APO-WARFARIN. |
Anticoagulants Platelet antiaggregants Thrombolytics Serotonin reuptake inhibitors | CT CT C CT | May increase bleeding risk. | Bleeding risk is increased when these drugs are used concomitantly with warfarin, closely monitor patients receiving any such class of drug with APO-WARFARIN. Adjust dosage accordingly or discontinue if necessary. |
| Nonsteroidal anti-inflammatory drugs (NSAIDs) | C, CT | May affect prothrombin time. May inhibit platelet aggregation. May cause gastrointestinal bleeding, peptic ulceration and/or perforation. May increase bleeding risk. | Close monitoring of patients receiving nonsteroidal anti-inflammatory agents (NSAIDs) is recommended to be certain that no change in anticoagulation dosage is required. Bleeding risk is increased when these drugs are used concomitantly with warfarin. Adjust dosage accordingly or discontinue if necessary. Consult the labeling of all concurrently used drugs to obtain further information about interactions with APO-WARFARIN or adverse reactions pertaining to bleeding. |
Legend: C = Case Study; CT = Clinical Trial
The following factors, alone or in combination, may be responsible for INCREASED PT ratio or INR, or INCREASED risk of bleeding:
Table 3 - ENDOGENOUS FACTORS that may be Responsible for Increased PT ratio or INR
| blood dyscrasias | diarrhea | hyperthyroidism |
| cancer | elevated temperature | poor nutritional state |
| collagen vascular disease | hepatic disorders (infectious hepatitis, jaundice) | steatorrhea |
| congestive heart failure | vitamin K deficiency |
EXOGENOUS FACTORS
Potential drug interactions with APO-WARFARIN are listed below by drug class and by specific drugs.
Table 4 - Classes of Drugs that may Interact with APO-WARFARIN and be Responsible for Increased PT ratio or INR
| 5-lipoxygenase Inhibitors | Adrenergic Stimulants, Central Alcohol Abuse Reduction Preparations | Analgesics |
| Anaesthetics, Inhalation | Antiandrogens | Antiarrhythmics * |
| Antibiotics * Aminoglycosides (oral) Cephalosporins (parenteral) Macrolides | Anticoagulants | Anticonvulsants * |
Penicillins (intravenous), high dose Quinolones (fluoroquinolones) Sulfonamides (long acting) Tetracyclines | ||
| Antidepressants * | Anti-fungal Medications, Intravaginal, Systemic* | Antimalarial Agents |
| Antineoplastics* | Antiparasitic/Antimicrobials | Antiplatelet Drugs/Effects |
| Antithyroid Drugs * | Beta-Adrenergic Blockers | Cholelitholytic Agents |
Diabetes Agents, Oral Diuretics * | Gastric Acidity and Peptic Ulcer Agents * | Gastrointestinal, Ulcerative Colitis Agents |
| Gastrointestinal, Prokinetic Agents | Gout Treatment Agents | Hemorrheologic Agents |
| Hepatotoxic Drugs | Hyperglycemic Agents | Hypertensive Emergency Agents |
| Hypnotics * | Leukotriene Receptor Antagonists | Lipid Lowering Agents* Bile Acid-Binding Resins* Fibrates HMG-CoA Reductase Inhibitors* |
| Monoamine Oxidase Inhibitors | Narcotics, prolonged | Natural medicines |
Nonsteroidal Anti-Inflammatory Agents Cox-2 Inhibitors Nonselective NSAIDS | Psychostimulants | Pyrazolones |
| Salicylates | Selective Serotonin Reuptake Inhibitors | Steroids, Adrenocortical * |
Steroids, Anabolic (17-Alkyl Testosterone Derivatives) | Thrombolytics | Thyroid Drugs |
| Tuberculosis Agents * | Uricosuric Agents | Vaccines |
| Vitamins * | ||
Table 5 - Specific Drugs that may Interact with APO-WARFARIN and be Responsible for Increased PT ratio or INR
acetaminophen (paracetamol) | alcohol* | allopurinol | aminosalicylic acid | amiodarone HCl |
| amoxicillin | argatroban | ASA (acetylsalicylic acid) | azithromycin | bezafibrate |
| benzbromarone | benziodarone | bivalirudin | capecitabine | carboplatin |
| cefaclor | cefamandole | cefazolin | cefixime | cefonicid |
| cefoperazone | cefotetan | cefotiam | cefoxitin | ceftriaxone |
| cefuroxime | celecoxib | chenodiol | chloramphenicol | chloral hydrate* |
| chlorpropamide | cholestyramine* | cimetidine | ciprofibrate | ciprofloxacin |
| cisapride | citalopram | clarithromycin | clofibrate | APO-WARFARIN overdose |
| cyclophosphamide* | danazol | danshen (Chinese herb) | desirudin | dextran |
| dextrothyroxine | diazoxide | diclofenac | dicumarol | diflunisal |
| disulfiram | doxycycline | econazole | erythromycin | escitalopram |
| esomeprazole | ethacrynic acid | ezetimibe | fenofibrate | fenoprofen |
| fluconazole | fluorouracil | fluoxetine | flutamide | fluvastatin |
| fluvoxamine | gatifloxacin | gefitinib | gemfibrozil | glucagon |
| glucosamine | halothane | heparin | ibuprofen | ifosfamide |
| indomethacin | influenza virus vaccine | itraconazole | ketoconazole | ketoprofen |
| ketorolac | lansoprazole | leflunomide | lepirudin | levamisole |
| levofloxacin | levothyroxine | liothyronine | lovastatin | medroxyprogeste rone |
mefenamic acid | megestrol | memantine | metandienone | methimazole* |
| methyldopa | methyl prednisolone | methylphenidate | Methylsalicylate ointment (topical) | metronidazole |
miconazole (intravaginal, oral, systemic*) | moricizine hydrochloride* | moxifloxacin | nalidixic acid | naproxen |
| neomycin | norfloxacin | noscapine | ofloxacin | olsalazine |
| omeprazole | orlistat | oxandrolone | oxaprozin | Oxolamine |
| oxymetholone | paclitaxel | pantoprazole | paroxetine | penicillin G, intravenous |
| pentoxifylline | phenylbutazone | phenytoin* | piperacillin | piroxicam |
| prasugrel | pravastatin | prednisone* | propafenone | propoxyphene |
| propranolol | propylthiouracil* | quinidine | quinine | rabeprazole |
| ranitidine* | rofecoxib | roxithromycin | sertraline | simvastatin |
| stanozolol | streptokinase | sulfamethizole | sulfamethoxazole | sulfinpyrazone |
| sulfisoxazole | sulindac | tamoxifen | tegafur | telithromycin |
| tetracycline | thyroid | ticarcillin | Tienilic acid | ticlopidine |
tissue plasminogen activator (t-PA) | tolbutamide | tolterodine | toremifene | tramadol |
trimethoprim /sulfamethoxazole | urokinase | valproate | vitamin E | voriconazole |
| zafirlukast |
also: other medications affecting blood elements which may modify
hemostasis dietary deficiencies; prolonged hot weather; unreliable PT determinations
* Increased and decreased PT ratio/INR responses have been reported.
The following factors, alone or in combination, may be responsible for DECREASED PT ratio or INR, or increased potential risk of thromboembolic events:
Table 6 - ENDOGENOUS FACTORS that may be Responsible for Decreased PT ratio or INR
| edema | hyperlipemia |
| hereditary coumarin resistance | hypothyroidism |
| nephrotic syndrome |
EXOGENOUS FACTORS
Potential drug interactions with APO-WARFARIN are listed below by drug class and by specific drugs
Table 7 - Classes of Drugs that may Interact with APO-WARFARIN and be Responsible for Decreased PT ratio or INR
| Adrenal Cortical Steroid Inhibitors | Antacids | Antianxiety Agents |
| Antiarrhythmics* | Antibiotics* | Anticonvulsants* |
| Antidepressants* | Anti-fungal Medications, Systemic* | Antihistamines |
| Antineoplastics* | Antipsychotic Medications | Antithyroid Drugs* |
| Barbiturates | Diuretics* | Enteral Nutritional Supplements |
| Enzyme inhibitors | Gastric Acidity and Peptic Ulcer Agents* | Hypnotics* |
| Immunosuppressives | Lipid Lowering Agents Bile Acid-Binding Resins* HMG-CoA Reductase Inhibitors* | Natural medicines |
Oral Contraceptives, Estrogen Containing Selective Estrogen Receptor Modulators Steroids, Adrenocortical* | Tuberculosis Agents* | Vitamins* |
Table 8 - Specific Drugs Reported to Interact with APO-WARFARIN and be Responsible for Decreased PT ratio or INR
| alcohol* | aminoglutethimide | amobarbital |
| aprepitant | atorvastatin | azathioprine |
| bosentan | butabarbital | butalbital |
| carbamazepine | chloral hydrate* | chlordiazepoxide |
| chlorthalidone | cholestyramine* | corticotropin |
| cortisone | APO-WARFARIN underdosage | cyclophosphamide* |
| dicloxacillin | ethchlorvynol | fosaprepitant |
| glutethimide | griseofulvin | haloperidol |
| meprobamate | 6-mercaptopurine | methimazole* |
| moricizine hydrochloride* | nafcillin | paraldehyde |
| pentobarbital | phenobarbital | phenytoin* |
| prednisone* | primidone | propylthiouracil* |
| raloxifene | rifampin | rifapentine |
| ranitidine* | secobarbital | spironolactone |
| sucralfate | trazodone | vitamin C (high dose) |
| vitamin K |
also: diet high in vitamin K; unreliable PT determinations
* Increased and decreased PT ratio/INR responses have been reported.
9.5. Drug-Food Interactions
Some foods (eg, certain green vegetables such as broccoli which are rich in vitamin K) can interact with APO-WARFARIN. Other foods may interact with APO-WARFARIN through CYP450 interactions (eg, grapefruit juice).
Cranberry juice and other cranberry products may also interact with APO-WARFARIN.
9.6. Drug-Herb Interactions
Natural Medicines (Including Herbals and Botanicals)
Caution should be exercised when natural medicines are taken concomitantly with APO-WARFARIN. Few, adequate, well-controlled studies exist evaluating the potential for metabolic and/or pharmacologic interactions between natural medicines and warfarin sodium. Due to a lack of manufacturing standardization with natural medicines, the amount of active ingredients may vary. This could further confound the ability to assess potential interactions and effects on anticoagulants. It is good practice to monitor the patient’s response with additional PT/INR determinations when initiating or discontinuing natural medicines.
Specific natural medicines reported to affect warfarin sodium therapy include the following:
- Bromelains, danshen, dong quai (Angelica sinensis), garlic, and Ginkgo biloba, ginseng, and cranberry products are associated most often with an INCREASE in the effects of APO-WARFARIN. However, the effects of ginseng can be variable (increased or decreased effect of warfarin sodium) and the combination should be avoided or more careful monitoring is warranted.
- Coenzyme Q10 (ubidecarenome) and St. John’s wort are associated most often with a DECREASE in the effects of warfarin sodium.
- Echinacea has also been reported to interact with warfarin sodium.
Some natural medicines may cause bleeding events when taken alone (e.g., garlic and Ginkgo biloba) and may have anticoagulant, antiplatelet, and/or fibrinolytic properties. These effects would be expected to be additive to the anticoagulant effects of APO-WARFARIN. Conversely, other natural medicines may have coagulant properties when taken alone or may decrease the effects of APO-WARFARIN.
Some natural medicines that may affect coagulation are listed below for reference; however, this list should not be considered all-inclusive. Many natural medicines have several common names and scientific names. The most widely recognized common natural medicines names are listed.
Table 9 - Natural medicines that contain coumarins with potential anticoagulant effects:
| Agrimonya (Argimonia eupatoria) | Licoriced (Glycyrrhiza globra) |
| Alfalfa (Medicago sativa) | Meadowsweetb (Spiræa ulmaria) |
| Aniseed (Pimpinella anisum) | Nettle (Urtica dioica) |
| Arnica | Parsley (Carum petroselinum) |
| Asa Foetida (Asafetida) | Passion Flower (Passiflora edulis) |
| Bogbeanb (Menyanthis folium) | Prickley Ash - Northern (Zanthoxylum americanum) |
| Peumus Boldo | Quassia (Amara) |
| Buchu (Barosmae boldo) | Red Clover (Trifolium pratense) |
| Paprika (Capsicum) | Sweet Clover (Melilotus officinalis) |
| Cassiac | Sweet Woodruff (Galii odorati herba) |
| Celery (Apium graveolens) | Tonka Beans (Dipteryx odorata) |
Chamomile - German and Roman (Anthemis nobilis) | Wild Carrot (Daucus carota) Wild Lettuce (Lactuca virosa) |
| Dandelionc (Taraxacum officinale) | Dong Quai (Angelica sinensis) |
| Fenugreek (Trigonella fœnumgræcum) | Horse Chestnut (Æsculus hippocastanum) |
| Horseradish (Cochleria armoracia) |
Miscellaneous natural medicines with anticoagulant properties:
Bladder Wrack (Fucus vesiculosus) Pau d’arco (Tabebuia avellanedæ)
Table 10 - Natural medicines that contain salicylate and/or have antiplatelet properties:
| Agrimonya | Ginger |
| Aloe Gel | Ginko Biloba |
| Aspen (Populus tremuloides) | Ginseng (Panax spp)e |
| Black Cohosh (Cimicifuga racemosa) | Licoricec |
| Black Haw (Viburnum prunifolium) | Meadowsweetb |
| Bogbeanb | Onione (Allium cepa) |
| Cassiad | Policosanol |
| Clove (Eugenia caryophyllus) | Poplar (Populi gemma) |
| Cranberry | Senega (Polygala) |
| Dandeliond | Tamarind (Tamarindus Indica) |
| Feverfew (Chrysanthenum parthenum) | Willow (Salix nigra) |
| Garlice (Tremuloides) | Wintergreen (Gaultheria procumbens) |
| German Sarsaparilla (Corex arenaria) |
Table 11 - Natural medicines with fibrinolytic properties:
| Bromelains (Bromelainum) | Ginseng (Panax spp)e |
| Capsicumc | Inositol Nicotinate |
| Garlice | Onione |
Table 12 - Natural medicines with coagulant properties:
| Green vegetables | Goldenseal (Chrysanthenum) |
| Mistletoe (Viscum album) | St John’s wort (hypericum perforatum) |
| Yarrow (Achillea millefolium) |
a Contains coumarins, has antiplatelet properties, and may have coagulant properties due to possible vitamin K content.
b Contains coumarins and salicyclate.
c Contains coumarins and has fibrinolytic properties.
d Contains coumarins and has antiplatelet properties.
e Has antiplatelet and fibrinolytic properties.
9.7. Drug-Laboratory Test Interactions
Interactions with laboratory tests have not been established.
10. Clinical Pharmacology
10.1. Mechanism of Action
Warfarin sodium and other coumarin anticoagulants act by inhibiting the synthesis of Vitamin K dependent clotting factors, which include Factors II, VII, IX and X, and the anticoagulant proteins C and S. Half-lives of these clotting factors are as follows: Factor II: 60 hours, VII: 4 to 6 hours, IX: 24 hours, and X: 48 to 72 hours. The half-lives of proteins C and S are approximately 8 hours and 30 hours, respectively. The resultant in vivo effect is a sequential depression of Factors VII, IX, X and II. Vitamin K is an essential cofactor for the post ribosomal synthesis of the vitamin K dependent clotting factors. The vitamin promotes the biosynthesis of g-carboxyglutamic acid residues in the proteins which are essential for biological activity. Warfarin is thought to interfere with clotting factor synthesis by inhibition of the regeneration of vitamin K1 epoxide. The degree of depression is dependent upon the dosage administered. Therapeutic doses of warfarin decrease the total amount of the active form of each vitamin K dependent clotting factor made by the liver by approximately 30% to 50%.
10.2. Pharmacodynamics
An anticoagulation effect generally occurs within 24 hours after drug administration. However, peak anticoagulant effect may be delayed 72 to 96 hours. The duration of action of a single dose of racemic warfarin is 2 to 5 days. The effects of warfarin sodium may become more pronounced as effects of daily maintenance doses overlap. Anticoagulants have no direct effect on an established thrombus, nor do they reverse ischemic tissue damage. However, once a thrombus has occurred, the goal of anticoagulant treatment is to prevent further extension of the formed clot and prevent secondary thromboembolic complications which may result in serious and possibly fatal sequelae.
10.3. Pharmacokinetics
APO-WARFARIN is a racemic mixture of the R- and S-enantiomers. The S-enantiomer exhibits 2 to 5 times more anticoagulant activity than the R-enantiomer in humans, but generally has a more rapid clearance. It is important that all warfarin sodium products provide the same ratio of enantiomers as that which is present in APO-WARFARIN.
Absorption
Warfarin sodium is essentially completely absorbed after oral administration with peak concentration generally attained within the first 4 hours. Studies using warfarin sodium indicate the rate but not the extent of absorption of the drug is decreased by the presence of food in the GI tract. Warfarin is also absorbed percutaneously. Individuals differ in the rate at which they absorb warfarin.
Distribution
There are no differences in the apparent volumes of distribution after intravenous and oral administration of single doses of warfarin solution. Warfarin distributes into a relatively small apparent volume of distribution of about 0.14 litre/kg. A distribution phase lasting 6 to 12 hours is distinguishable after rapid intravenous or oral administration of an aqueous solution. Using a one compartment model, and assuming complete bioavailability, estimates of the volumes of distribution of R- and S-warfarin are similar to each other and to that of the racemate. Warfarin is distributed to the liver, lungs, spleen, kidney, and crosses the placenta. Concentrations in fetal plasma approach the maternal values, but warfarin has not been found in human milk (see 7.1.2 Breastfeeding). Approximately 99% of the drug is bound to plasma proteins.
Metabolism
Individual patients vary greatly in the rate at which they metabolize warfarin. The elimination of warfarin is almost entirely by metabolism. Warfarin sodium is stereoselectively metabolized by hepatic microsomal enzymes (cytochrome P-450) to inactive hydroxylated metabolites (predominant route) and by reductases to reduced metabolites (warfarin alcohols). The warfarin alcohols have minimal anticoagulant activity. The metabolites are principally excreted into the urine; and to a lesser extent into the bile. The metabolites of warfarin that have been identified include dehydrowarfarin, two diastereoisomer alcohols, 4'-, 6-, 7-, 8- and 10-hydroxywarfarin.
Numerous cytochrome p-450 isozymes may be involved in the metabolism of warfarin, including CYP 2C9, 2C19, 2C8, 2C18, 1A2 and 3A4. CYP 2C9 is likely to be the principal isozyme modulating anticoagulant activity in clinical use. This enzyme constitutes the primary pathway for the metabolism of S-warfarin, the more potent enantiomer found in racemic mixtures of warfarin. Its complete inhibition in vivo may be expected to result in lower maintenance dose requirement of warfarin. Individuals with allelic polymorphisms of CYP 2C9 have been identified and have been shown to have lower maintenance dose requirements of warfarin and increased risk of overanticoagulation.
The S-enantiomer of warfarin is mainly metabolized to 7-hydroxywarfarin by CYP2C9, a polymorphic enzyme. The variant alleles CYP2C9*2 and CYP2C9*3 result in decreased in vitro CYP2C9 enzymatic 7-hydroxylation of S-warfarin. The frequencies of these allelles in Caucasians are approximately 11% and 7% for CYP2C9*2 and CYP2C9*3, respectively. Patients with one or more of these variant CYP2C9 alleles have decreased S-warfarin clearance (Table 13).
Table 13 - Relationship between S-Warfarin Clearance and CYP2C9 Genotype in Caucasian Patients
| CYP2C9 Genotype | N | S-Warfarin Clearance/Lean Body Weight (mL/min/kg) Mean (SD)a |
|---|---|---|
| *1/*1 | 118 | 0.065 (0.025) b |
| *1/*2 or *1/*3 | 59 | 0.041 (0.021) b |
| *2/*2, *2/*3 or *3/*3 | 11 | 0.020 (0.011) b |
| Total | 188 |
aSD=standard deviation.
b p<0.001. Pairwise comparisons indicated significant differences among all 3 genotypes.
Other CYP2C9 alleles associated with reduced enzymatic activity occur at lower frequencies, including *5, *6, and *11 alleles in populations of African ancestry and *5, *9 and *11 alleles in Caucasians.
Elimination
The terminal half-life of warfarin after a single dose is approximately one week; however, the effective half-life ranges from 20 to 60 hours, with a mean of about 40 hours. The clearance of R-warfarin is generally half that of S-warfarin, thus as the volumes of distribution are similar, the half-life of R-warfarin is longer than that of S-warfarin. The half-life of R-warfarin ranges from 37 to 89 hours, while that of S-warfarin ranges from 21 to 43 hours. Studies with radiolabeled drug have demonstrated that up to 92% of the orally administered dose is recovered in urine. Very little warfarin is excreted unchanged in urine. Urinary excretion is in the form of metabolites.
Special Populations and Conditions:
- Geriatrics: Patients 60 years or older appear to exhibit greater than expected PT/INR response to the anticoagulation effects of warfarin. The cause of this increased sensitivity in this age group is not known. This increased anticoagulant effect of warfarin may be due to a combination of pharmacokinetic and pharmacodynamic factors. Racemic warfarin clearance may be unchanged or reduced with increasing age. Limited information suggest that there is no difference in the clearance of S-warfarin in the elderly, compared to that seen in young subjects. However, there may be a slight decrease in the clearance of R-warfarin in the elderly, compared to the young. Therefore, as patient age increases, a lower dose of warfarin is usually required to produce a therapeutic level of anticoagulation.
Genetic Polymorphism: A meta-analysis of 9 qualified studies including 2775 patients (99% Caucasian) was performed to examine the clinical outcomes associated with CYP2C9 gene variants in warfarin-treated patients. In this meta-analysis, 3 studies assessed bleeding risks and 8 studies assessed daily dose requirements. The analysis suggested an increased bleeding risk for patients carrying either the CYP2C9*2 or CYP2C9*3 alleles. Patients carrying at least one copy of the CYP2C9*2 allele required a mean daily warfarin dose that was 17% less than the mean daily dose for patients homozygous for the CYP2C9*1 allele. For patients carrying at least one copy of the CYP2C9*3 allele, the mean daily warfarin dose was 37% less than the mean daily dose for patients homozygous for the CYP2C9*1 allele.
In an observational study, the risk of achieving INR >3 during the first 3 weeks of warfarin therapy was determined in 219 Swedish patients retrospectively grouped by CYP2C9 genotype. The relative risk of over anticoagulation as measured by INR >3 during the first 2 weeks of therapy was approximately doubled for those patients classified as *2 or *3 compared to patients who were homozygous for the *1 allele.
Warfarin reduces the regeneration of vitamin K from vitamin K epoxide in the vitamin K cycle, through inhibition of vitamin K epoxide reductase (VKOR), a multiprotein enzyme complex.
Certain single nucleotide polymorphisms in the VKORC1 gene (especially the -1639G>A allele) have been associated with lower dose requirements for warfarin. In 201 Caucasian patients treated with stable warfarin doses, genetic variations in the VKORC1 gene were associated with lower warfarin doses. In this study, about 30% of the variance in warfarin dose could be attributed to variations in the VKORC1 gene alone; about 40% of the variance in warfarin dose could be attributed to variations in VKORC1 and CYP2C9 genes combined. About 55% of the variability in warfarin dose could be explained by the combination of VKORC1 and CYP2C9 genotypes, age, height, body weight, interacting drugs, and indication for warfarin therapy in Caucasian patients. Similar observations have been reported in Asian patients.
- Hepatic Insufficiency: Hepatic dysfunction can potentiate the response to warfarin through impaired synthesis of clotting factors and decreased metabolism of warfarin.
- Renal Insufficiency: Renal clearance is considered to be a minor determinant of anticoagulant response to warfarin.
- Storage, Stability, and Disposal
Protect from light and moisture. Store at room temperature 15˚C to 30˚C.
Dispense in a tight, light-resistant container as defined in the U.S.P.
12. Special Handling Instructions
Warfarin is absorbed percutaneously.
Pharmacy and clinical personnel who are pregnant should avoid exposure to crushed or broken tablets. See 7.1.1 Pregnancy.
Part 2: Scientific Information
13. Pharmaceutical Information
Drug Substance
Proper name: Warfarin sodium, U.S.P. (crystalline)
Chemical name: 3-( α -acetonyl-benzyl)-4-hydroxycoumarin
Molecular formula and molecular mass: C19H15NaO4 and 330.31 g/mol
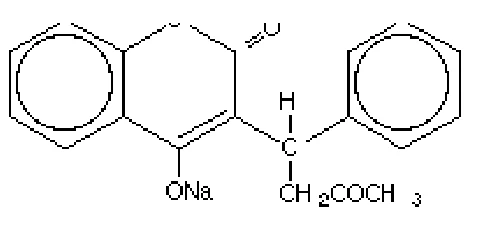
Structural formula:
Physicochemical properties:
Description: Crystalline warfarin sodium, U.S.P., a vitamin K dependent factor anticoagulant, is chemically crystalline sodium warfarin isopropanol clathrate. Warfarin is a coumarin derivative and is available as a racemic mixture of the 2 optical isomers of the sodium salt. The crystallization of warfarin sodium virtually eliminates trace impurities present in amorphous warfarin sodium, thus achieving a crystalline product of the highest purity. Warfarin sodium occurs as a white, odourless, crystalline powder which has a slightly bitter taste, is discoloured by light and is very soluble in water; freely soluble in alcohol; very slightly soluble in chloroform and in ether. The pH is between 7.2 and 8.3, in a solution (1 in 100). The melting point is between 157° to 167°C, range not to exceed 4°C. The pKa is 5.05.
Pharmaceutical standard: USP
14. Clinical Trials
14.2. Comparative Bioavailability Studies
Four comparative bioavailability studies were performed using fed or fasted healthy human volunteers. The rate and extent of absorption of warfarin was measured and compared following oral administration of a 2 or 10 mg dose of APO-WARFARIN or COUMADIN (1 or 10 mg) tablets. The results from measured data are summarized as follows:
Fasting Study: Summary Table of the Comparative Bioavailability Data Warfarin (2 x 1 mg) From Measured Data | |||
| Parameter | Geometric Mean Arithmetic Mean (CV%) | Ratio of Geometric Means (%)** | |
| APO-WARFARIN 1 mg | COUMADIN®† 1 mg | ||
AUC0-72 (ng·hr/mL) AUCI (ng·hr/mL) Cmax (ng/mL) Tmax (hr)* t½ (hr)* | 4289 4396 (24) 7400 7764 (33) 234 239 (20) 0.50 (55) 60.4 (28) | 4508 4591 (20) 7740 7908 (21) 241 246 (21) 0.48 (35) 60.2 (24) | 95.7 96.5 97.3 -- -- |
* Arithmetic means (CV%). ** Based on the least squares estimate. † COUMADIN® is manufactured by DuPont Pharma, and was purchased in Canada. | |||
Fed Study: Summary Table of the Comparative Bioavailability Data Warfarin (2 x 1 mg) From Measured Data | |||
| Parameter | Geometric Mean Arithmetic Mean (CV%) | Ratio of Geometric Means (%)** | |
| APO-WARFARIN 1 mg | COUMADIN®† 1 mg | ||
AUC0-72 (ng·hr/mL) AUCI (ng·hr/mL) Cmax (ng/mL) Tmax (hr)* t½ (hr)* | 3992 4045 (17) 6951 7173 (26) 120 121 (13) 2.47 (52) 61.0 (30) | 4166 4236 (19) 7415 7756 (31) 125 127 (16) 2.94 (42) 62.7 (33) | 94.7 90.2 95.4 -- -- |
* Arithmetic means (CV%). ** Based on the least squares estimate. † COUMADIN® is manufactured by DuPont Pharma, and was purchased in Canada. | |||
Fasting Study: Summary Table of the Comparative Bioavailability Data Warfarin (1 x 10 mg) From Measured Data | |||
| Parameter | Geometric Mean Arithmetic Mean (CV%) | Ratio of Geometric Means (%)** | |
| APO-WARFARIN 10 mg | COUMADIN®† 10 mg | ||
AUC0-72 (mcg·hr/mL) AUCI (mcg·hr/mL) Cmax (mcg/mL) Tmax (hr)* t½ (hr)* | 31.7 32.0 (16) 42.4 43.7 (28) 1.17 1.19 (20) 1.27 (130) 36.8 (22) | 31.4 31.8 (16) 41.5 42.6 (25) 1.30 1.32 (15) 0.78 (47) 35.2 (23) | 99.1 99.2 89.2 -- -- |
* Arithmetic means (CV%). ** Based on the least squares estimate. † COUMADIN® is manufactured by DuPont Pharma, and was purchased in Canada. | |||
Fed Study: Summary Table of the Comparative Bioavailability Data Warfarin (1 x 10 mg) From Measured Data | |||
| Parameter | Geometric Mean Arithmetic Mean (CV%) | Ratio of Geometric Means (%)** | |
| APO-WARFARIN 10 mg | COUMADIN®† 10 mg | ||
AUC0-72 (mcg·hr/mL) AUCI (mcg·hr/mL) Cmax (mcg/mL) Tmax (hr)* t½ (hr)* | 32.5 33.0 (18) 43.3 44.5 (24) 0.963 0.975 (17) 3.18 (43) 35.8 (19) | 32.8 33.1 (15) 43.8 44.6 (20) 0.956 0.970 (17) 4.10 (42) 35.7 (17) | 99.1 98.9 100.7 -- -- |
* Arithmetic means (CV%). ** Based on the least squares estimate. † COUMADIN® is manufactured by DuPont Pharma, and was purchased in Canada. | |||
15. Microbiology
No microbiological information is required for this drug product.
16. Non-Clinical Toxicology
Carcinogenicity
Carcinogenicity and mutagenicity studies have not been performed with warfarin sodium.
Reproductive and developmental toxicology
The reproductive effects of warfarin have not been evaluated.
Warfarin is contraindicated in women who are or who may become pregnant because the drug passes through the placental barrier and may cause fatal hemorrhage to the fetus in utero. Furthermore, there have been reports of birth malformations in children born to mothers who have been treated with warfarin during pregnancy. See 2 Contraindications and 7.1.1 Pregnancy.
- 17. Supporting Product Monograph
COUMADIN (warfarin sodium tablets), 1 mg, 2 mg, 2.5 mg, 3 mg, 4 mg, 5 mg, 6 mg and 10 mg, control number 217553, Product Monograph, Bristol-Myers Squibb Canada. (2018-09-04)