


Product Monograph - Atovaquone and Proguanil Hydrochloride Tablets
CLINICAL PHARMACOLOGY
Pharmacokinetics
There are no pharmacokinetic interactions between atovaquone and proguanil at the recommended dose. A population pharmacokinetic analysis in adults and children was used to characterize the pharmacokinetics of atovaquone and proguanil.
Table 1 summarizes the pharmacokinetic parameters from an atovaquone-proguanil interaction study using dose levels of Atovaquone and Proguanil Hydrochloride Tablets utilized in the treatment of malaria.
Table 1: Atovaquone, Proguanil and Cycloguanil Geometric Mean Parameters and Point Estimates for Atovaquone and Proguanil Hydrochloride Tablets (4 x 250 mg Atovaquone / 100 mg Proguanil HCl) versus Atovaquone Tablets (4 x 250 mg) alone, and Proguanil HCl Tablets (4 x 100 mg) alone in Healthy Adults following
Daily Administration for 3 Days in the Fed State
| Parameter | Geometric means | Combined/Alone ratio x 100 (%) | 90% Confidence Interval (%) | ||||||||
|---|---|---|---|---|---|---|---|---|---|---|---|
| Combined | Alone | ||||||||||
| Atovaquone | |||||||||||
AUC0-24 (h.µg/mL)1 | 193 | 180 | 108 | (100, 116) | |||||||
AUC∞ (h.µg/mL)2 | 510 | 549 | 93 | (79, 110) | |||||||
cmax (µg/mL) | 11.5 | 10.5 | 110 | (102, 118) | |||||||
| t½ (h) | 59 | 57.1 | 103 | (96, 111) | |||||||
| Proguanil (PG) | |||||||||||
AUC0-24 (h.µg/mL)1 | 5.82 | 6.30 | 92 | (86, 99) | |||||||
AUC∞ (h.µg/mL)2 | 6.00 | 6.44 | 93 | (84, 103) | |||||||
cmax (µg/mL) | 0.509 | 0.548 | 93 | (87, 99) | |||||||
| t½ (h) | 14.5 | 13.7 | 106 | (100, 113) | |||||||
| Cycloguanil (CG) | |||||||||||
AUC0-24 (h.µg/mL)1 | 1.19 | 1.30 | 92 | (86, 98) | |||||||
AUC∞ (h.µg/mL)2 | 1.20 | 1.36 | 89 | (79, 99) | |||||||
cmax (µg/mL) | 0.0792 | 0.0821 | 97 | (92, 101) | |||||||
| t½ (h) | 11.8 | 11.1 | 106 | (93, 120) | |||||||
| AUCCG/AUCPG3 | 0.21 | 0.22 | 94 | (86, 103) | |||||||
1 AUC0-24 : Trapezoidal area under plasma curve from last dose until 24h post dose.
2 AUC0-∞ : Trapezoidal area under plasma curve from last dose until final measured concentration, extrapolated from last concentration to infinity, corrected for concentration pre-dose. At true steady state, this is equivalent to AUC0-∞ for a single dose.
3 Ratio of AUC0-∞ for cycloguanil to proguanil.
Absorption: Atovaquone is a highly lipophilic compound with low aqueous solubility. The pharmacokinetics of atovaquone are comparable between healthy subjects and HIV-infected patients. Although there are no absolute bioavailability data for atovaquone in healthy subjects, in HIV-infected patients the absolute bioavailability of a 750 mg single dose of atovaquone tablets taken with food is 21% (90% CI: 17% - 27%). Dietary fat taken with atovaquone increases the rate and extent of absorption. When taken with a standard breakfast containing 23 g of fat, AUC was increased 2-3 times and Cmax 5 times compared to the fasting state. Patients should take atovaquone and proguanil hydrochloride tablets with food or a milky drink (see DOSAGE AND ADMINISTRATION).
Proguanil hydrochloride is rapidly and extensively absorbed regardless of food intake.
Distribution: The apparent volume of distribution of atovaquone and proguanil is a function of body weight. Atovaquone is highly protein bound (> 99%) but does not displace other highly protein bound drugs in vitro, indicating that significant drug interactions arising from displacement are unlikely. The volume of distribution of atovaquone following oral administration in both adults and children is approximately
8.8 L/kg. Proguanil is 75% protein bound. The volume of distribution of proguanil following oral administration is 42 to 27 L/kg in adults (weighing 41-80 kg). In human plasma the binding of atovaquone and proguanil were unaffected by the presence of the other.
Metabolism: There is no evidence that atovaquone is metabolised and there is negligible excretion of atovaquone in urine with the parent drug being predominantly (> 90%) eliminated unchanged in faeces.
Proguanil hydrochloride is partially metabolised with less than 40% being excreted unchanged in the urine. Proguanil is metabolized to cycloguanil (primarily via CYP2C19) and 4-chlorophenylbiguanide, and these are also excreted unchanged in the urine.
Elimination: The oral clearance of atovaquone and proguanil is a function of body weight. The elimination half-life of atovaquone is about 2-3 days in adults and 1-2 days in children 6 to 12 years of age. The elimination half-lives of proguanil and cycloguanil are about 12-15 hours in both adults and children 6 to 12 years of age. Following oral administration, the clearance of atovaquone in adults and children (weighing 41-80 kg) is approximately 0.16 to 0.05 L/h/kg. Following oral administration, the clearance of proguanil in adults (weighing 41-80 kg) is 1.6 to 0.85 L/h/kg.
Special Populations
Renal Impairment: There are no studies in children with renal impairment. The effect of renal impairment was evaluated after single-dose oral administration of atovaquone and proguanil hydrochloride tablets in adults. In patients with mild to moderate renal impairment, oral clearance and/or AUC data for atovaquone, proguanil, and cycloguanil are within the range of values observed in patients with normal renal function. In patients with severe renal impairment (creatinine clearance < 30 mL/min), atovaquone Cmax and AUC are reduced, while the elimination half-lives for proguanil and cycloguanil are prolonged, with corresponding increases in AUC, resulting in the potential for drug accumulation with repeated dosing (see CONTRAINDICATIONS and PRECAUTIONS, Renal Impairment).
Hepatic Impairment: There are no studies in children with hepatic impairment. In a single-dose study, the pharmacokinetics of atovaquone, proguanil, and cycloguanil were compared in 13 adult patients with hepatic impairment (9 mild, 4 moderate, as indicated by the Child-Pugh method) with 13 adult subjects with normal hepatic function. In patients with mild or moderate hepatic impairment there were no marked differences in the rate or extent of systemic exposure to atovaquone (based on Cmax, Tmax, and AUC values). There was also no marked difference in the elimination half-life of atovaquone in these patients. There were no marked changes in the Cmax, Tmax, and elimination half- life of proguanil in patients with mild or moderate hepatic impairment. However, there was a marked increase (85%) in proguanil AUC in these patients, which is not considered to be clinically relevant due to proguanil’s wide therapeutic range.
Consistent with the increase in proguanil AUC, there were marked decreases in the systemic exposure to cycloguanil (Cmax and AUC). This was particularly evident in patients with moderate hepatic impairment, where few measurable cycloguanil concentrations were seen. The decrease in the systemic exposure to cycloguanil is unlikely to be clinically relevant based on evidence from in vitro and clinical data (in more than 100 patients), which indicate that phenotypic status of proguanil metabolism (i.e., low exposure to cycloguanil in poor metabolizers) does not influence the efficacy of atovaquone and proguanil hydrochloride tablets (see PRECAUTIONS, Hepatic Impairment).
The pharmacokinetics of atovaquone and proguanil hydrochloride tablets has not been studied in patients with severe hepatic impairment.
Elderly Subjects: A single oral dose pharmacokinetic study indicates that no dosage adjustments are needed in the healthy elderly. There is no clinically significant change in the average rate or extent of absorption of atovaquone or proguanil between healthy elderly and young patients. Systemic availability of cycloguanil is higher in the elderly compared to young subjects, but there is no clinically significant change in its elimination half-life. However, since geriatric patients may have reduced renal function, caution should be taken when treating geriatric patients with atovaquone and proguanil hydrochloride tablets (see PRECAUTIONS, Use in Elderly and Renal Impairment, and CLINICAL PHARMACOLOGY, Special Populations, Renal Impairment).
Pediatrics: The pharmacokinetics of atovaquone, proguanil, and cycloguanil were characterized following the daily oral administration of separate tablets of atovaquone and proguanil hydrochloride for 3 consecutive days. The dose was based on body weight. The pharmacokinetics of proguanil and cycloguanil were found to be similar in adult and pediatric patients. However, the elimination half-life of atovaquone was shorter in pediatric patients (1 to 2 days) than in adult patients (2 to 3 days), resulting in a lower Cmax and AUC in children (i.e., lower systemic exposure to atovaquone in children than in adults). Clinical cure rates, however, were not affected.
Clinical Studies
The prophylaxis indication for adults weighing above 40 kg is based on 3 placebo- controlled studies of 10 to 12 weeks duration conducted in endemic areas with over 700 subjects and 2 active-controlled studies in non-immune travellers which enrolled more than 2000 non-immune travellers to a malaria-endemic country.
The treatment indication is based on 5 controlled clinical studies conducted in 466 patients (adults and children) receiving concurrent atovaquone and proguanil hydrochloride at the recommended dose (see DOSAGE AND ADMINISTRATION). Most of the patients were residents of malaria-endemic areas and may have had previous malaria infections that could have conferred a degree of immunity.
INDICATIONS AND CLINICAL USE
Prevention of Malaria: Atovaquone and proguanil hydrochloride tablets are indicated for the prophylaxis of P. falciparum malaria including areas where chloroquine resistance has been reported.
Treatment of Malaria: Atovaquone and proguanil hydrochloride tablets are indicated for the treatment of acute, uncomplicated P.falciparum malaria when oral treatment is appropriate.
Atovaquone and proguanil hydrochloride tablets have been shown to be effective in areas where P. falciparum may be resistant to some other antimalarials.
CONTRAINDICATIONS
Atovaquone and proguanil hydrochloride tablets are contraindicated in individuals with known hypersensitivity to atovaquone or proguanil hydrochloride or any component of the formulation (see PHARMACEUTICAL INFORMATION, Composition).
Atovaquone and proguanil hydrochloride tablets are contraindicated for prophylaxis of P. falciparum malaria in patients with severe renal impairment (creatinine clearance < 30 mL/min). In patients with severe renal impairment, an alternative to Atovaquone and proguanil hydrochloride tablets should be recommended for treatment of P. falciparum malaria whenever possible (see CLINICAL PHARMACOLOGY, Special Populations, Renal Impairment, and PRECAUTIONS, Renal Impairment).
WARNINGS
Serious hypersensitivity reactions, including angioedema and anaphylaxis, have been reported rarely following the use of atovaquone and proguanil hydrochloride tablets for treatment and prophylaxis of malaria. These reactions may occur after the administration of the first dose. In this event, atovaquone and proguanil hydrochloride tablets should be discontinued immediately and supportive medical treatment should be sought.
Atovaquone and proguanil hydrochloride tablets have not been evaluated for the treatment of cerebral malaria or other severe manifestations of complicated malaria including hyperparasitemia, pulmonary oedema or renal failure. Patients with severe malaria are not candidates for oral therapy.
In the event of recrudescent infections due to P. falciparum, or failure of chemoprophylaxis, patients should be treated with a different antimalarial.
Absorption of atovaquone may be reduced in patients with diarrhoea or vomiting, but diarrhoea or vomiting was not associated with reduced efficacy in clinical trials of atovaquone and proguanil hydrochloride tablets for malaria prophylaxis. Persons taking atovaquone and proguanil hydrochloride tablets for prophylaxis or treatment of malaria should take a repeat dose if they vomit within 1 hour of dosing. In the event of diarrhoea, normal dosing should be continued. As with other antimalarial agents, patients with diarrhoea or vomiting should be reminded to continue to comply with personal protection measures (repellants, bednets).
In patients with acute malaria who present with diarrhoea or vomiting, alternative therapy should be considered. If atovaquone and proguanil hydrochloride tablets are used to treat malaria in these patients, parasitemia should be closely monitored.
Parasitemia should be closely monitored in patients receiving concurrent tetracycline or metoclopramide (see PRECAUTIONS, Drug Interactions).
The concomitant administration of atovaquone and proguanil hydrochloride tablets and rifampicin or rifabutin is not recommended (see PRECAUTIONS, Drug Interactions).
PRECAUTIONS
General
Patients who have a history of epilepsy or psychiatric illness should take atovaquone and proguanil hydrochloride tablets with caution. During clinical trials, one adult and one child receiving atovaquone/proguanil hydrochloride for the treatment of malaria had seizures; the child successfully continued treatment. Both subjects had a prior history of seizures and the investigators did not consider the events to be exacerbated by treatment with atovaquone and proguanil hydrochloride tablets. Two adult subjects receiving atovaquone monotherapy experienced psychiatric symptoms. One subject had a history of psychiatric illness and the other a history of drug and alcohol abuse (see ADVERSE REACTIONS).
Absorption of orally administered atovaquone is significantly reduced when fasting. Therefore alternative therapy with other agents should be considered for patients who are not able to consume food (see CLINICAL PHARMACOLOGY, Pharmacokinetics, Absorption).
Parasite relapse occurred commonly when P. vivax malaria was treated with atovaquone and proguanil hydrochloride tablets alone. Travellers with intense exposure to P. vivax or P. ovale, and those who develop malaria caused by either of these parasites, will require additional treatment with a drug, such as primaquine, that is active against hypnozoites.
Use in the Elderly
A single-dose pharmacokinetic study indicates that no dosage adjustments are needed in the healthy elderly (see CLINICAL PHARMACOLOGY, Special Populations, Elderly Subjects).
Use in Pregnant Women
There are no studies in pregnant women. The safety of atovaquone and proguanil hydrochloride tablets when administered concurrently for use in human pregnancy has not been established. Atovaquone and proguanil hydrochloride tablets should be considered for use in pregnancy only if the expected benefit to the mother justifies the potential risk to the foetus.
Reproductive toxicity studies in animals did not indicate any teratogenic potential at dosages of atovaquone:proguanil hydrochloride of up to 50:20 mg/kg/day in the rat or 100:40 mg/kg/day in the rabbit. In rabbits given atovaquone alone at doses up to 1,200 mg/kg/day, an increased incidence of resorptions and decrease in length and weight of fetuses was noted. These effects were likely to be secondary to toxicity of atovaquone in maternal animals. However, animal studies are not always predictive of human response.
The proguanil component of atovaquone and proguanil hydrochloride tablets acts by inhibiting parasitic dihydrofolate reductase. There are no clinical data indicating that folate supplementation diminishes drug efficacy. For women of childbearing age receiving folate supplements to prevent neural tube birth defects, such supplements may be continued while taking atovaquone and proguanil hydrochloride tablets.
Use in Nursing Mothers
It is not recommended that mothers receiving atovaquone and proguanil hydrochloride tablets breastfeed their babies. It is not known whether atovaquone is excreted in human milk. Proguanil is excreted in human milk in small quantities. In a rat study, the atovaquone concentrations in milk were 30% of the concurrent atovaquone concentrations in maternal plasma.
The amount of atovaquone or proguanil found in human breast milk would not provide adequate treatment for the infant against malaria.
Use in Children
Treatment of Malaria
Atovaquone and proguanil hydrochloride tablets are not recommended for treatment of acute, uncomplicated P.falciparum malaria in children who weigh less than 40 kg.
Renal Impairment
There are no studies in children with renal impairment (see CLINICAL PHARMACOLOGY, Special Populations, Renal Impairment).
A single-dose pharmacokinetic study in adults indicates that no special precautions or dosage adjustments are needed in patients with mild to moderate renal impairment.
Atovaquone and proguanil hydrochloride tablets are not recommended in patients with severe renal impairment (see CLINICAL PHARMACOLOGY, Special Populations, Renal Impairment, and CONTRAINDICATIONS).
Hepatic Impairment
There are no studies in children with hepatic impairment (see CLINICAL PHARMACOLOGY, Special Populations, Hepatic Impairment).
A single dose pharmacokinetic study in adults indicates that no dosage adjustments are needed in patients with mild to moderate hepatic impairment. No studies have been conducted in patients with severe hepatic impairment (see CLINICAL PHARMACOLOGY, Special Populations, Hepatic Impairment).
Drug Interactions
General
Atovaquone is highly protein bound (> 99%) but does not displace other highly protein bound drugs in vitro, indicating that significant drug interactions arising from displacement are unlikely. Proguanil is metabolized primarily by CYP2C19. Potential pharmacokinetic interactions with other substrates or inhibitors of this pathway are unknown.
Use with Anticoagulants
Proguanil may potentiate the anticoagulant effect of warfarin and other coumarin based anticoagulants. The mechanism of this potential drug interaction has not been established. Caution is advised when initiating or withdrawing malaria prophylaxis or treatment with atovaquone-proguanil in patients on continuous treatment with coumarin based anticoagulants.
Use with Efavirenz
Coadministration of efavirenz with atovaquone and proguanil hydrochloride tablets resulted in a decrease in exposures to atovaquone and proguanil. When given with efavirenz or boosted protease-inhibitors, atovaquone concentrations have been observed to decrease as much as 75%. Since decreased concentrations of atovaquone and proguanil may result in a decrease of antimalarial efficacy, concomitant administration should be avoided whenever possible.
Use with Rifampicin, Rifabutin, Tetracycline or Metoclopramide
Parasitemia should be closely monitored in patients receiving tetracycline or metoclopramide concurrently with atovaquone and proguanil hydrochloride tablets.
The concomitant administration of atovaquone and proguanil hydrochloride tablets and rifampicin or rifabutin is not recommended.
Concomitant treatment with tetracycline, metoclopramide, rifabutin and rifampicin has been associated with significant decreases in plasma concentrations of atovaquone. Increased clearance of atovaquone when coadministered with tetracycline, leading to 40% lower atovaquone concentrations, has been observed. Concomitant administration of rifampicin or rifabutin is known to reduce atovaquone levels by approximately 50% and 34% respectively.
Use with Indinavir
Concomitant administration of atovaquone and indinavir results in a decrease in the Cmin of indinavir (23% decrease; 90% CI 8-35%). Caution should be exercised when prescribing atovaquone with indinavir due to the decrease in trough levels of indinavir.
Use with Other Antimalarial Agents
Atovaquone and proguanil hydrochloride tablets should not be administered in combination with other antimalarial drugs. Interactions between atovaquone and proguanil hydrochloride tablets and other antimalarial drugs have not been studied.
ADVERSE REACTIONS
As atovaquone and proguanil hydrochloride tablets contains atovaquone and proguanil hydrochloride, the type and severity of adverse reactions associated with each of the compounds may be expected. At the doses employed for the treatment and prophylaxis of malaria, adverse reactions have generally been mild and of limited duration. There has been no evidence of increased toxicity following concurrent administration of the two compounds.
A summary of adverse events associated with the use of atovaquone and proguanil hydrochloride tablets, atovaquone, or proguanil hydrochloride is provided below.
Blood and Lymphatic: Anemia, neutropenia. Pancytopenia in patients with severe renal impairment
Endocrine and Metabolic: Anorexia, hyponatremia
Gastrointestinal: Abdominal pain, nausea, vomiting, diarrhoea, gastric intolerance, oral ulceration, stomatitis
Hepatobiliary Tract and Pancreas: Elevated liver enzyme levels and reports of hepatitis, cholestasis, elevated amylase levels. Clinical trial data for atovaquone and proguanil hydrochloride tablets indicated that abnormalities in liver function tests (elevated bilirubin and transaminases) were reversible and not associated with untoward clinical events.
Immune System/Hypersensitivity: Allergic reactions: including rash, urticaria, pruritus, angioedema, isolated reports of anaphylaxis, and vasculitis.
Lower Respiratory: Cough
Neurology: Headache, insomnia, dizziness, asthenia
Non-Site Specific: Fever
Skin: Rash, hair loss
Other events seen in clinical trials with atovaquone and proguanil hydrochloride tablets include:
Body as a Whole: Back pain, lethargy
Cardiovascular: Hypotension, palpitations
Erythropoietic: Splenomegaly
Gastrointestinal: Hepatomegaly, constipation, dyspepsia
Musculoskeletal: Myalgia
Neurology: Strange or vivid dreams, visual difficulties, depression, anxiety
Of the seven severe or treatment-limiting adverse experiences reported in clinical trials with atovaquone and proguanil hydrochloride, three were considered to be treatment related; two were reports of nausea and/or vomiting and one, a report of an anaphylactic reaction (see WARNINGS). Two subjects, one adult and one 4-year-old child, receiving atovaquone/proguanil hydrochloride for the treatment of malaria had seizures; the child successfully continued treatment. Both subjects had a prior history of seizures and the investigators did not consider the events to be exacerbated by treatment with atovaquone and proguanil hydrochloride tablets. During clinical trials, two adult subjects receiving atovaquone monotherapy experienced psychiatric symptoms. One subject had a history of psychiatric illness and the other a history of drug and alcohol abuse. Studies of this size and design would only be able to detect adverse events at a rate of 1:150 (95% CI).
Treatment
Table 2 provides a summary of the adverse events considered by investigators to be attributable to study medication and reported in clinical trials for the treatment of malaria with atovaquone and proguanil hydrochloride tablets. Abdominal pain, headache, anorexia, nausea, vomiting, diarrhoea, asthenia and abnormal liver function tests were the most commonly reported adverse experiences.
Table 2 : Adverse Events Considered by Investigators to be Attributable to Study Medication, Occurring in ≥ 1% of Adults with Malaria in Completed Phase III Treatment Studies
| Adverse Event | Atovaquone and Proguanil Hydrochloride Tablets (n = 304) | PYR + S (n = 81) | MFQ (n = 91) | ADQ (n = 71) | C±PYR+S* (n = 55) |
| Gastrointestinal | |||||
| Abdominal Pain | 15%(45) | 21%(17) | 0% | 8%(6) | 0% |
| Vomiting | 12%(35) | 15%(12) | 0% | 25%(18) | 2%(1) |
| Nausea | 11%(32) | 14%(11) | 2% (2) | 21% (15) | 2%(1) |
| Diarrhoea | 8%(25) | 11%(9) | 0% | 7% (5) | 2%(1) |
| Anorexia | 5%(15) | 5%(4) | 1%(1) | 13%(9) | 2%(1) |
| Hepatomegaly | 2%(6) | 6% (5) | 0% | 0% | 0% |
| Constipation | 1%(2) | 0% | 0% | 0% | 0% |
| Dyspepsia | 1%(2) | 0% | 0% | 0% | 0% |
| Nervous/Psychiatric | |||||
| Headache | 8%(25) | 31%(25) | 1% (1) | 7%(5) | 0% |
| Dizziness | 3%(8) | 11%(9) | 0% | 11%(8) | 2%(1) |
| Insomnia | 1%(3) | 4%(3) | 0% | 25%(18) | 0% |
| Body as a Whole | |||||
| Asthenia | 7%(20) | 16%(13) | 0% | 3%(2) | 0% |
| Back Pain | 1%(2) | 4%(3) | 0% | 0% | 0% |
| Abnormal liver function tests | |||||
| ALT | 6%(18) | 6%(5) | 7%(6) | 0% | 0% |
| AST | 5%(16) | 5%(4) | 7%(6) | 0% | 0% |
| Bilirubin | 2%(7) | 0% | 1%(1) | 0% | 0% |
| Cardiovascular | |||||
| Hypotension, postural | 2%(6) | 17%(14) | 0% | 0% | 0% |
| Palpitations | 2%(5) | 0% | 0% | 6%(4) | 0% |
| Cutaneous | |||||
| Pruritus | 2%(6) | 2%(2) | 0% | 46%(33) | 0% |
| Rash | 1%(2) | 0% | 0% | 0% | 0% |
| Musculoskeletal | |||||
| Myalgia | 3%(8) | 6%(5) | 0% | 4%(3) | 0% |
| Erythropoietic | |||||
| Splenomegaly | 1%(4) | 2%(2) | 0% | 0% | 0% |
| Respiratory | |||||
| Coughing | 1%(3) | 0% | 0% | 2%(2) | 0% |
PYR = pyrimethamine S = sulfadoxine MFQ = mefloquine ADQ = amodiaquine C= chloroquine
* Data for both comparator groups of chloroquine alone plus pyrimethamine and sulfadoxine.
A similar profile of clinical adverse events was reported in children with malaria treated with atovaquone and proguanil hydrochloride in phase III trials as occurred in the adult studies.
Prophylaxis
In clinical trials of atovaquone and proguanil hydrochloride tablets for prophylaxis of malaria in adults weighing above 40 kg, the most commonly reported adverse events, independent of attributability, were headache, abdominal pain and diarrhoea, and were reported in a similar proportion of subjects receiving atovaquone and proguanil hydrochloride tablets or placebo.
Table 3 provides a summary of the most common drug-related adverse events reported in clinical trials of Atovaquone and Proguanil Hydrochloride Tablets for the prophylaxis of malaria in non- immune travellers weighing above 40 kg.
Table 3: Common Drug-Related, Treatment-Emergent Adverse Events (≥5%) in Non-Immune Travellers Weighing Above 40 kg (Atovaquone and Proguanil Hydrochloride Tablets vs Mefloquine and Atovaquone and Proguanil Hydrochloride Tablets vs Chloroquine/Proguanil)
| Adverse Event | Atovaquone and Proguanil Hydrochloride Tablets 1 (n=993) | Mefloquine2 (n=471) | Chloroquine3/ Proguanil4 (n=511) | ||||||||||
Active5 n (%) | All6 n (%) | Active5 n (%) | All6 n (%) | Active5 n (%) | All6 n (%) | ||||||||
| Any Adverse Event | 256 | 336 | 204 | 205 | 142 | 142 | |||||||
| (26) | (34) | (43) | (44) | (28) | (28) | ||||||||
| Digestive System | 135 | 173 | 94 | 96 | 100 | 100 | |||||||
| (14) | (17) | (20) | (20) | (20) | (20) | ||||||||
| Neuro-Psychiatric* | 117 | 165 | 139 | 139 | 53 | 54 | |||||||
| (12) | (17) | (30) | (30) | (10) | (11) | ||||||||
| Body as a Whole | 55 | 84 | 58 | 58 | 34 | 34 | |||||||
| (6) | (8) | (12) | (12) | (7) | (7) | ||||||||
| Skin and Appendages | 32 | 39 | 23 | 23 | 14 | 14 | |||||||
| (3) | (4) | (5) | (5) | (3) | (3) | ||||||||
* Neuro-Psychiatric adverse events include strange or vivid dreams, dizziness, insomnia, visual difficulties, psychiatric depression and anxiety.
11-2 days before travel until 7 days after travel.
2Weekly from 1-3 weeks before travel until 4 weeks after travel.
31 week before until 4 weeks after travel.
41-2 days before travel until 4 weeks after travel.
5Active - includes adverse events that occurred while the active study drug was being administered.
6All - includes adverse events that occurred while any study drug (active or placebo) was being administered.
Post-Marketing Adverse Reactions: In addition to adverse events reported from clinical trials, the following events have been identified during worldwide post-approval use of atovaquone and proguanil hydrochloride tablets. Because they are reported voluntarily from a population of unknown size, estimates of frequency cannot be made. These events have been chosen for inclusion due to a combination of their seriousness, frequency of reporting, or potential causal connection to atovaquone and proguanil hydrochloride tablets.
Skin: Cutaneous reactions ranging from rash, photosensitivity, and urticaria to cases of erythema multiforme and Stevens-Johnson syndrome.
Central Nervous System: Cases of seizures and psychotic events (such as hallucinations); however, a causal relationship has not been established.
Hypersensitivity: Allergic reactions: including rash, urticaria, pruritis, angioedema and isolated reports of anaphylaxis (see WARNINGS).
Hepatobiliary Tract and Pancreas: Elevated liver enzyme levels and reports of hepatitis, elevated amylase levels.
SYMPTOMS AND TREATMENT OF OVERDOSAGE
| For management of a suspected drug overdose, contact your regional Poison Control Centre. |
There is limited information regarding overdosage from the administration of atovaquone and proguanil hydrochloride tablets. In cases of suspected overdosage symptomatic and supportive therapy should be given as appropriate.
There is no known antidote for atovaquone, and it is currently unknown if atovaquone is dialyzable. The median lethal dose is higher than the maximum oral dose tested in mice and rats (1,825 mg/kg/day). Overdoses up to 31,500 mg of atovaqone have been reported. In one such patient who also took an unspecified dose of dapsone, methemoglobinemia occurred. Rash has also been reported after overdose.
Overdoses of proguanil hydrochloride as large as 1,500 mg have been followed by complete recovery, and doses as high as 700 mg twice daily have been taken for over 2 weeks without serious toxicity. Adverse events occasionally associated with proguanil hydrochloride doses of 100 to 200 mg/day, such as epigastric discomfort and vomiting, would be likely to occur with overdose. There are also reports of reversible hair loss and scaling of the skin on the palms and/or soles, reversible aphthous ulceration, and hematologic side effects.
DOSAGE AND ADMINISTRATION
Each atovaquone and proguanil hydrochloride tablet contains 250 mg of atovaquone and 100 mg proguanil hydrochloride.
The daily dose should be taken with food or a milky drink (to ensure maximum absorption) at the same time each day (see PRECAUTIONS, General). In the event of vomiting within 1 hour of dosing a repeat dose should be taken. Should vomiting continue, alternative therapy should be considered or the patient’s parasitemia should be monitored.
Atovaquone and proguanil hydrochloride tablets should preferably be swallowed whole. The tablets may be crushed and mixed with condensed milk just prior to administration for patients who may have difficulty swallowing tablets.
PROPHYLAXIS
Prophylaxis with atovaquone and proguanil hydrochloride tablets should start 1 to 2 days before entering a malaria endemic area and any other non-endemic area where prophylaxis for malaria is recommended by international travel Health Authorities (such as PHAC, CDC, WHO, etc.). Prophylaxis should be continued daily throughout the stay and for 7 additional days after leaving the area of concern.
Dosage in Adults
One atovaquone and proguanil hydrochloride tablet (adult strength = 250 mg atovaquone and 100 mg proguanil hydrochloride) daily.
TREATMENT
Dosage in Adults
Four atovaquone and proguanil hydrochloride tablets (adult strength) as a single dose for three consecutive days.
Dosage in Children (see PRECAUTIONS, Use in Children, and CLINICAL PHARMACOLOGY, Special Populations, Pediatrics)
The dosage for treatment of acute malaria in children is based upon body weight.
> 40 kg: Dose as for adults; Four atovaquone and proguanil hydrochloride tablets (adult strength= 250 mg atovaquone and 100 mg proguanil hydrochloride) as a single dose for three consecutive days.
SPECIAL POPULATIONS
Patients with Renal Impairment: There are no studies in children with renal impairment. However, pharmacokinetic studies in adults indicate that no dosage adjustments are needed in patients with mild to moderate renal impairment.
Atovaquone and proguanil hydrochloride tablets should not be used for malaria prophylaxis in patients with severe renal impairment (creatinine clearance < 30 mL/min), and alternatives to atovaquone and proguanil hydrochloride tablets should be recommended for treatment of acute P. falciparum malaria whenever possible (see CONTRAINDICATIONS, PRECAUTIONS, Renal Impairment, and CLINICAL PHARMACOLOGY, Special Populations).
Patients with Hepatic Impairment: There are no studies in children with hepatic impairment. However, a pharmacokinetic study in adults indicates that no dosage adjustments are needed in patients with mild to moderate hepatic impairment. No studies have been conducted in patients with severe hepatic impairment (see PRECAUTIONS, Hepatic Impairment, and CLINICAL PHARMACOLOGY, Special Populations).
PHARMACEUTICAL INFORMATION
Drug Substance
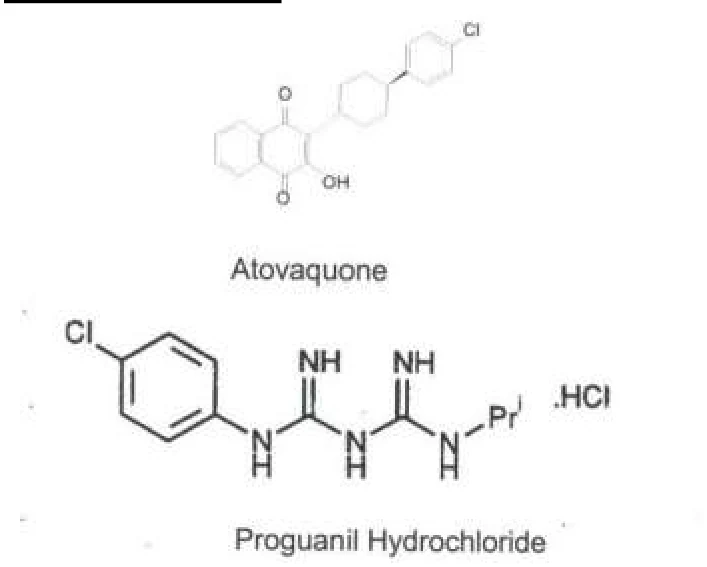
Proper Name: Atovaquone + Proguanil Hydrochloride
Chemical Name:
Atovaquone: trans-2-[4-(4-chlorophenyl)-cyclohexyl]-3-hydroxy-1,4- naphtalenedione
Proguanil Hydrochloride: 1-(4-chlorophenyl)-5-isopropyl-biguanide hydrochloride
Structural Formula:
| Molecular Formula: | Atovaquone: | C22H19Cl03 |
| Proguanil: | C11H16ClN5.HCl | |
| Molecular Weight: | Atovaquone: | 366.84 |
| Proguanil hydrochloride: | 290.2 |
Description:
Atovaquone: Atovaquone is a yellow powder with a melting point of ≈ 221°C. It is insoluble in water and in 0.1 M HCl, and very slightly soluble in 0.1 M NaOH.
Proguanil Hydrochloride: A white crystalline powder, with a melting point of 239°C to 245°C. It is slightly soluble in water and sparingly soluble in alcohol. It is practically insoluble in methylene chloride.
Comparative Bioavailability Studies
A single oral dose crossover comparative bioavailability study comparing Atovaquone and Proguanil Hydrochloride (250 mg Atovaquone /100 mg Proguanil Hydrochloride Tablets), Glenmark Pharmaceuticals Canada Inc. with MALARONE® (250 mg Atovaquone + 100 mg Proguanil Hydrochloride) tablets (GlaxoSmithKline Inc.) was conducted in 68 healthy Asian male subjects (from 19 to 40 years of age) under fasting conditions. Bioavailability data were measured and the results from 62 subjects are summarized in Table 4 for Atovaquone; the results from the first 40 subjects to complete the study are summarized in Table 5 for Proguanil.
Table 4: SUMMARY TABLE OF THE COMPARATIVE BIOAVAILABILITY
DATA FOR ATOVAQUONE
Atovaquone (1 x 250 mg) From measured data Geometric Mean Arithmetic Mean (CV %) | ||||
|---|---|---|---|---|
| Parameter | Test* | Reference† | % Ratio of Geometric Means | 90% Confidence Interval |
AUC0-336 (ng.hr/mL) | 39449.07 44807.17 (46.4) | 40796.29 45681.90 (49.9) | 96.70 | 86.73-107.81 |
AUC0-72¥ (ng.hr/mL) | 19061.95 20826.29 (36.7) | 19769.96 21412.82 (40.5) | 96.42 | 86.61-107.34 |
Cmax (ng/mL) | 558.97 613.44 (43.3) | 603.31 650.70 (40.5) | 92.65 | 83.75-102.50 |
Tmax# (hr) | 3.00 (1.33 - 48.00) | 3.00 (1.33 - 48.00) | ||
* Atovaquone and Proguanil Hydrochloride (250 mg Atovaquone /100 mg Proguanil Hydrochloride Tablets), Glenmark Pharmaceuticals Canada Inc.
† MALARONE® (250 mg Atovaquone + 100 mg Proguanil Hydrochloride) tablets, manufactured by GlaxoSmithKline Inc., was purchased in Canada.
# Expressed as the median (range) only
Atovaquone: N=62
¥ n=46 for AUC0-72
Atovaquone: N=62
Note: Due to long half-life of atovaquone, AUC∞ and T1/2 are not reported due to inability to accurately estimate the terminal elimination phase.
Table 5: SUMMARY TABLE OF THE COMPARATIVE BIOAVAILABILITY
DATA FOR PROGUANIL
Proguanil (1 x 100 mg) From measured data Geometric Mean Arithmetic Mean (CV %) | ||||
|---|---|---|---|---|
| Parameter | Test* | Reference† | % Ratio of Geometric Means | 90% Confidence Interval |
AUCT (ng.hr/mL) | 2218.61 2353.02 (33.6) | 2241.98 2365.68 (31.4) | 98.96 | 96.47 – 101.51 |
AUC∞ (ng.hr/mL) | 2294.05 2432.07 (33.6) | 2310.89 2435.43 (31.2) | 99.27 | 96.93 – 101.67 |
Cmax (ng/mL) | 122.50 124.32 (17.2) | 124.37 127.16 (20.3) | 98.49 | 95.08 – 102.03 |
Tmax# (hr) | 3.00 (1.33 - 6.00) | 2.50 (1.00 - 6.00) | ||
T½2 (hr) | 18.72 (19.12) | 18.69 (18.84) | ||
* Atovaquone and Proguanil Hydrochloride (250 mg Atovaquone /100 mg Proguanil Hydrochloride Tablets), Glenmark Pharmaceuticals Canada Inc.
† MALARONE® (250 mg Atovaquone + 100 mg Proguanil Hydrochloride) tablets, manufactured by GlaxoSmithKline Inc., was purchased in Canada.
# Expressed as the median (range) only
2 Expressed as the arithmetic mean (CV %) only
Proguanil: N=40
Composition
Each atovaquone and proguanil hydrochloride tablet contains 250 mg of atovaquone and 100 mg proguanil hydrochloride.
The non-medicinal ingredients in the tablet are low-substituted hydroxypropyl cellulose, magnesium stearate, microcrystalline cellulose, poloxamer 188, povidone K30, colloidal silicon dioxide and sodium starch glycollate. The tablet coating contains hypromellose, titanium dioxide, polyethylene glycol 400, polyethylene glycol 8000 and iron oxide red.
Stability and Storage Recommendations
Store between 15°C - 30°C.
AVAILABILITY OF DOSAGE FORMS
Atovaquone and proguanil hydrochloride tablets, 250 mg/100 mg are pinkish brown to brown colored, circular, biconvex beveled edged film coated tablets with ‘404’ debossed on one side and ‘G’ debossed on the other side. They are available in bottles of 100 tablets and cartons of 12 tablets (each carton contains 1 blister pack of 12 tablets).