


Product Monograph - Auro-Candesartan HCT
RECENT MAJOR LABEL CHANGES
| 7 Warnings and Precautions – Carcinogenesis and Mutagenesis, Ophthalmologic, Skin | 05/2022 |
|---|---|
| 7 Warnings and Precautions – Respiratory | 10/2023 |
TABLE OF CONTENTS
Sections or subsections that are not applicable at the time of authorization are not listed.
RECENT MAJOR LABEL CHANGES ............................................................................................. 2
TABLE OF CONTENTS ............................................................................................................... 2
PART I: HEALTH PROFESSIONAL INFORMATION ....................................................................... 4
1 INDICATIONS ........................................................................................................................ 4
1.1 Pediatrics ......................................................................................................................... 4
1.2 Geriatrics ......................................................................................................................... 4
2 CONTRAINDICATIONS ........................................................................................................... 4
3 SERIOUS WARNINGS AND PRECAUTIONS BOX ...................................................................... 5
4 DOSAGE AND ADMINISTRATION ........................................................................................... 5
4.1 Dosing Considerations ..................................................................................................... 5
4.2 Recommended Dose and Dosage Adjustment ................................................................ 5
4.4 Administration ................................................................................................................. 6
4.5 Missed Dose .................................................................................................................... 7
5 OVERDOSAGE ....................................................................................................................... 7
6 DOSAGE FORMS, STRENGTHS, COMPOSITION AND PACKAGING .......................................... 7
7 WARNINGS AND PRECAUTIONS ............................................................................................ 8
7.1 Special Populations ....................................................................................................... 13
7.1.1 Pregnant Women ....................................................................................................... 13
7.1.2 Breast-feeding ............................................................................................................ 14
7.1.3 Pediatrics .................................................................................................................... 14
7.1.4 Geriatrics .................................................................................................................... 14
8 ADVERSE REACTIONS .......................................................................................................... 14
8.1 Adverse Reaction Overview ........................................................................................... 14
8.2 Clinical Trial Adverse Reactions ..................................................................................... 15
8.3 Less Common Clinical Trial Adverse Reactions .............................................................. 17
8.4 Abnormal Laboratory Findings: Hematologic, Clinical Chemistry and Other Quantitative Data ..................................................................................................................................... 18
8.5 Post-Market Adverse Reactions .................................................................................... 19
9 DRUG INTERACTIONS .......................................................................................................... 20
9.1 Serious Drug Interactions .............................................................................................. 20
9.2 Drug Interactions Overview ........................................................................................... 20
9.3 Drug-Behavioural Interactions ...................................................................................... 20
9.4 Drug-Drug Interactions .................................................................................................. 20
9.5 Drug-Food Interactions ................................................................................................. 26
9.6 Drug-Herb Interactions .................................................................................................. 26
9.7 Drug-Laboratory Test Interactions ................................................................................ 27
10 CLINICAL PHARMACOLOGY ............................................................................................... 27
10.1 Mechanism of Action .................................................................................................. 27
10.2 Pharmacodynamics ..................................................................................................... 28
10.3 Pharmacokinetics ........................................................................................................ 28
11 STORAGE, STABILITY AND DISPOSAL ................................................................................. 30
12 SPECIAL HANDLING INSTRUCTIONS................................................................................... 31
PART II: SCIENTIFIC INFORMATION ........................................................................................ 32
13 PHARMACEUTICAL INFORMATION.................................................................................... 32
14 CLINICAL TRIALS ................................................................................................................ 33
14.1 Clinical Trials by Indication .......................................................................................... 33
Essential Hypertension ........................................................................................................ 33
14.2 Comparative Bioavailability Studies ............................................................................ 34
15 MICROBIOLOGY ................................................................................................................ 37
16 NON-CLINICAL TOXICOLOGY ............................................................................................. 37
17 SUPPORTING PRODUCT MONOGRAPH ............................................................................. 42
PATIENT MEDICATION INFORMATION ................................................................................... 43
PART I: HEALTH PROFESSIONAL INFORMATION
1 INDICATIONS
Auro-Candesartan HCT (candesartan cilexetil/hydrochlorothiazide) is indicated for:
- the treatment of essential hypertension in patients for whom combination therapy is appropriate.
Auro-Candesartan HCT is not indicated for initial therapy (see 4 DOSAGE AND ADMINISTRATION).
The dosage of Auro-Candesartan HCT must be individualized. The dose of Auro-Candesartan HCT should be determined by titration of the individual components.
1.1 Pediatrics
Pediatrics (< 18 years of age): No data are available to Health Canada; therefore, Health Canada has not authorized an indication for pediatric use (see 7.1.3 Pediatrics).
1.2 Geriatrics
Geriatrics (> 65 years of age): No overall differences in safety or effectiveness were observed between the younger and elderly patients but greater sensitivity of some older patients cannot be ruled out and appropriate caution is recommended (see 7.1.4 Geriatrics).
2 CONTRAINDICATIONS
Auro-Candesartan HCT is contraindicated in:
- Patients who are hypersensitive to this drug or to any ingredient in the formulation, including any non-medicinal ingredient, or component of the container. For a complete listing, see 6 DOSAGE FORMS, STRENGTHS, COMPOSITION AND PACKAGING.
- Patients with anuria and patients who are hypersensitive to other sulfonamide-derived drugs, because of the hydrochlorothiazide component (see Immune and 8.5 Post-Market Adverse Reactions).
- Pregnant women (see 7.1.1 Pregnant Women).
- Nursing women (see 7.1.2 Breast-feeding).
- Children aged < 1 year.
- Combination with aliskiren-containing drugs in patients with diabetes mellitus (type 1 or type 2) or moderate to severe renal impairment (GFR < 60 mL/min/1.73m2) (see Dual blockade of the Renin-Angiotensin System (RAS), Renal, and 9.4 Drug-Drug Interactions).
- Patients with severe hepatic impairment and/or cholestasis.
- Patients with severe renal impairment (creatinine clearance < 30 mL/min/1.73 m2 BSA).
- Patients with gout.
- Patients with rare hereditary problems of galactose intolerance, the Lapp lactase deficiency or glucose-galactose malabsorption.
3 SERIOUS WARNINGS AND PRECAUTIONS BOX
Serious Warnings and Precautions
|
|---|
4 DOSAGE AND ADMINISTRATION
4.1 Dosing Considerations
- The dosage of Auro-Candesartan HCT (candesartan cilexetil/hydrochlorothiazide) must be individualized.
- The fixed combination is not for initial therapy.
- The dose of Auro-Candesartan HCT should be determined by titration of the individual components.
4.2 Recommended Dose and Dosage Adjustment
Once the patient has been stabilized on the individual components, one Auro-Candesartan HCT 16 mg / 12.5 mg, 32 mg / 12.5 mg or 32 mg / 25 mg tablet once daily may be taken if the doses on which the patient was stabilized are the same as those in the fixed combination (see 1 INDICATIONS).
Initiation of therapy requires consideration of recent antihypertensive treatment, the extent of blood pressure elevation, salt restriction, and other pertinent clinical factors.
Candesartan cilexetil Monotherapy
The recommended initial dose of candesartan cilexetil is 16 mg, once daily. Total daily doses of candesartan cilexetil should range from 8 to 32 mg. Doses higher than 32 mg do not appear to have a greater effect on blood pressure reduction, and there is relatively little experience with such doses. Most of the antihypertensive effect is present within 2 weeks and the maximal blood pressure reduction is generally obtained within 4 weeks. For patients with possible depletion of intravascular volume (e.g. patients treated with diuretics, particularly those with impaired renal function) consideration should be given to administration of a lower dose. If blood pressure is not controlled by candesartan cilexetil alone, a thiazide diuretic may be added (see 9.4 Drug- Drug Interactions).
Concomitant Diuretic Therapy
In patients receiving diuretics, candesartan cilexetil therapy should be initiated with caution, since these patients may be volume-depleted and thus more likely to experience hypotension following initiation of additional antihypertensive therapy.
Whenever possible, all diuretics should be discontinued two to three days prior to the administration of candesartan cilexetil, to reduce the likelihood of hypotension (see Hypotension). If this is not possible because of the patient's condition, candesartan cilexetil should be administered with caution and the blood pressure monitored closely. Thereafter, the dosage should be adjusted according to the individual response of the patient.
As a rule, concomitant diuretic therapy is not necessary when Auro-Candesartan HCT is used.
Dosage Adjustments in the Presence of Pathologies
Hepatic Impairment: Dose titration is recommended in patients with mild to moderate chronic liver disease.
Auro-Candesartan HCT is contraindicated in patients with severe hepatic impairment and/or cholestasis (see 2 CONTRAINDICATIONS).
Renal Impairment: In patients with mild to moderate renal impairment (i.e., creatinine clearance between 30-80 mL/min/1.73m2 BSA), a dose titration is recommended.
Auro-Candesartan HCT is contraindicated in patients with severe renal impairment (creatinine clearance < 30 mL/min/1.73 m2 BSA) (see 2 CONTRAINDICATIONS).
Dosage Adjustments in Special Populations
Pediatrics (< 18 years of age): Health Canada has not authorized an indication for pediatric use (see 7.1.3. Pediatrics).
Geriatrics (> 65 years of age): No dose adjustment of Auro-Candesartan HCT is necessary for elderly patients. As greater sensitivity of some older patients cannot be ruled out, appropriate caution is recommended (see 7.1.4 Geriatrics).
4.4 Administration
Auro-Candesartan HCT should be taken once daily, at approximately the same time each day, with or without food.
4.5 Missed Dose
If a patient misses a dose of Auro-Candesartan HCT and remembers within 12 hours, the patient should take the dose as soon as possible and then go back to the regular schedule. If it is more than 12 hours after the patient remembers, they should not take the missed dose; the next dose should be taken on time.
A double dose of Auro-Candesartan HCT should never be taken to make up for a missed dose.
5 OVERDOSAGE
No specific information is available on the treatment of overdosage with candesartan cilexetil/hydrochlorothiazide. Treatment is symptomatic and supportive.
Candesartan cilexetil
Limited data are available in regard to overdosage of candesartan cilexetil in humans. The most likely manifestations of overdosage would be hypotension, dizziness and tachycardia; bradycardia could occur from reflex parasympathetic (vagal) stimulation. Thirst, ventricular arrhythmias, sedation/impairment of consciousness and muscle cramps can also be observed. If symptomatic hypotension should occur, supportive treatment should be instituted and vital signs monitored. The patient should be placed supine with the legs elevated. If this is not sufficient, plasma volume should be increased by infusion of, for example, isotonic saline solution. Sympathomimetic drugs may also be administered if the above-mentioned measures are not sufficient. In case reports detailing overdosage (≤ 672 mg candesartan cilexetil) patient recovery was uneventful.
Candesartan cilexetil is not removed from the plasma by hemodialysis.
Hydrochlorothiazide
The most common symptoms observed from overdosage of hydrochlorothiazide are those caused by electrolyte depletion (hypokalemia, hypochloremia, hyponatremia) and dehydration resulting from excessive diuresis. If digitalis has also been administered, hypokalemia may accentuate cardiac arrhythmias. The degree to which hydrochlorothiazide is removed by hemodialysis has not been established.
| For management of a suspected drug overdose, contact your regional poison control centre. |
|---|
6 DOSAGE FORMS, STRENGTHS, COMPOSITION AND PACKAGING
Table 1 Dosage Forms, Strengths, and Composition
| Route of Administration | Dosage Form / Strength/Composition | Non-medicinal Ingredients |
|---|---|---|
| Oral Use | Tablet: 16 mg / 12.5 mg, 32 mg / 12.5 mg and 32 mg / 25 mg | Carmellose calcium, ferric oxide red (16 mg / 12.5 mg & 32 mg / 25 mg only), ferric oxide yellow, hydroxy propyl cellulose, Lactose monohydrate, magnesium alumino metasilicate type 1A, magnesium stearate and propylene glycol. |
Auro-Candesartan HCT (candesartan cilexetil / hydrochlorothiazide) is available in tablets of 16 mg / 12.5 mg, 32 mg / 12.5 mg and 32 mg / 25 mg.
Auro-Candesartan HCT 16 mg/12.5 mg tablets: Pink, uncoated capsule shaped tablets debossed with ‘J’ and ‘05’ separated by score line on one side and plain with score line on other side, available in blister packs of 30’s & HDPE bottles of 30’s, 100’s & 500’s count.
Auro-Candesartan HCT 32 mg/12.5 mg tablets: Yellow, uncoated oval shaped tablets debossed with ‘J’ and ‘07’ separated by score line on one side and plain with score line on other side, available in blister packs of 30’s & HDPE bottles of 30’s, 100’s & 500’s count.
Auro-Candesartan HCT 32 mg/25 mg tablets: Pink, uncoated oval shaped tablets debossed with ‘J’ and ‘15’ separated by score line on one side and plain with score line on other side, available in blister packs of 30’s & HDPE bottles of 30’s, 100’s & 500’s count.
7 WARNINGS AND PRECAUTIONS
Please see 3 SERIOUS WARNINGS AND PRECAUTIONS BOX.
Carcinogenesis and Mutagenesis
Non-melanoma skin cancer: An increased risk of non-melanoma skin cancer (NMSC) [basal cell carcinoma (BCC) and squamous cell carcinoma (SCC) of the skin] after hydrochlorothiazide therapy was reported in some epidemiological studies. The risk may be higher with increasing cumulative use (see 8.5 Post-Market Adverse Reactions). The photosensitizing action of hydrochlorothiazide may be a possible mechanism for NMSC (see Hydrochlorothiazide).
Patients taking hydrochlorothiazide should be informed of the potential risk of NMSC. They should be advised to regularly check their skin for new lesions as well as changes to existing ones, and to promptly report any suspicious skin lesions. Patients should also be advised to limit exposure to sunlight, to avoid the use of indoor tanning equipment, and to use adequate protection (e.g. a broad spectrum sunscreen with a SPF of 30 or higher, clothing, and a hat) when exposed to sunlight or UV light to minimize the risk of skin cancer.
Alternatives to hydrochlorothiazide may be considered for patients who are at a particularly high risk for NMSC (e.g., light coloured skin, known personal or family history of skin cancer, ongoing immunosuppressive therapy, etc.) (see 8.5 Post-Market Adverse Reactions).
Cardiovascular
Dual blockade of the Renin-Angiotensin System (RAS): There is evidence that co- administration of angiotensin receptor antagonists (ARBs), such as the candesartan cilexetil component of Auro-Candesartan HCT, or of angiotensin converting enzyme inhibitors (ACEIs) with aliskiren increases the risk of hypotension, syncope, stroke, hyperkalemia and deterioration of renal function, including renal failure, in patients with diabetes mellitus (type 1 or type 2) and/or moderate to severe renal impairment (GFR < 60 mL/min/1.73m2). Therefore, the use of Auro-Candesartan HCT in combination with aliskiren-containing drugs is contraindicated in these patients (see 2 CONTRAINDICATIONS).
Further, co-administration of ARBs, including the candesartan cilexetil component of Auro-Candesartan HCT, with other agents blocking the RAS, such as ACEIs or aliskiren-containing drugs, is generally not recommended in other patients, since such treatment has been associated with an increased incidence of severe hypotension, decreased renal function (including acute renal failure), and hyperkalemia.
Avoid the concomitant use of ACE inhibitors and ARBs in patients with diabetic nephropathy.
If dual blockade therapy is considered necessary, this should only occur under specialist supervision and subject to frequent close monitoring of renal function, electrolytes and blood pressure.
Hypotension: Occasionally, symptomatic hypotension has occurred after administration of candesartan cilexetil. It is more likely to occur in patients who are volume-depleted by diuretic therapy, dietary salt restriction, dialysis, diarrhea or vomiting, or undergoing surgery with anesthesia. In these patients, because of the potential fall in blood pressure, therapy should be started under close medical supervision. Similar considerations apply to patients with ischemic heart or cerebrovascular disease, in whom an excessive fall in blood pressure could result in myocardial infarction or cerebrovascular accident (see 8 ADVERSE REACTIONS).
Valvular Stenosis: There is concern on theoretical grounds that patients with aortic stenosis might be at particular risk of decreased coronary perfusion when treated with vasodilators because they do not develop as much afterload reduction.
Driving and Operating Machinery
The effect of candesartan cilexetil/hydrochlorothiazide on the ability to drive and use machines has not been studied, but based on its pharmacodynamic properties candesartan cilexetil/hydrochlorothiazide is unlikely to affect this ability. When driving vehicles or operating machines, it should be taken into account that occasionally dizziness or weariness may occur during treatment of hypertension. Exercise caution when driving or operating a vehicle or potentially dangerous machinery.
Endocrine and Metabolism
Metabolism: Patients receiving thiazides, including hydrochlorothiazide (HCTZ), should be carefully observed for clinical signs of fluid and electrolyte imbalance (hyponatremia, hypochloremic alkalosis and hypokalemia).
Periodic determinations of serum electrolytes, to detect possible electrolyte disturbance, should be performed at appropriate intervals. Warning signs or symptoms of fluid and electrolyte imbalance include dryness of the mouth, thirst, weakness, lethargy, drowsiness, restlessness, muscle pain or cramps, muscle fatigue, hypotension, oliguria, tachycardia and gastrointestinal disturbances such as nausea and vomiting.
Hypokalemia may develop, especially with brisk diuresis, when severe cirrhosis is present, or after prolonged therapy.
Interference with adequate oral electrolyte intake will also contribute to hypokalemia. Hypokalemia can sensitize or exaggerate the response of the heart to the toxic effects of digitalis (e.g. increased ventricular irritability).
Any chloride deficit during thiazide therapy is generally mild and usually does not require specific treatment except under extraordinary circumstances (as in liver disease or renal disease). Dilutional hyponatremia may occur in edematous patients in hot weather. Appropriate therapy is water restriction rather than administration of salt, except in rare instances, when the hyponatremia is life threatening. In actual salt depletion, appropriate replacement is the therapy of choice.
Hyperuricemia may occur or acute gout may be precipitated in certain patients receiving thiazide therapy.
Thiazides may decrease serum PBI (protein bound iodine) levels without signs of thyroid disturbance.
Thiazides have been shown to increase excretion of magnesium; this may result in hypomagnesemia.
Thiazides may decrease urinary calcium excretion and may cause intermittent and slight elevation of serum calcium in the absence of known disorders of calcium metabolism. Marked hypercalcemia may be evidence of hidden hyperparathyroidism. Thiazides should be discontinued before carrying out tests for parathyroid function.
Treatment with a thiazide diuretic may impair glucose tolerance (see 9.4 Drug-Drug Interactions). Increases in cholesterol and triglyceride levels may be associated with thiazide diuretic therapy. However, at the doses contained in candesartan cilexetil/hydrochlorothiazide, minimal effects were observed.
Hepatic/Biliary/Pancreatic
Hepatic Impairment: Thiazides should be used with caution in patients with impaired hepatic function or progressive liver disease, since minor alterations of fluid or electrolyte balance may precipitate hepatic coma.
Dose titration is recommended in patients with mild to moderate chronic liver disease (see Hepatic Impairment).
Auro-Candesartan HCT is contraindicated in patients with severe hepatic failure and/or cholestasis (see 2 CONTRAINDICATIONS).
No studies were carried out with candesartan cilexetil/hydrochlorothiazide fixed combination in patients with impaired hepatic function.
Immune
Hypersensitivity Reactions: Sensitivity reactions to hydrochlorothiazide may occur in patients with or without a history of allergy or bronchial asthma.
Systemic Lupus Erythematosus: The possibility of exacerbation or activation of systemic lupus erythematosus has been reported in patients treated with hydrochlorothiazide.
Ophthalmologic
Choroidal Effusion, Acute Myopia and Secondary Angle-Closure Glaucoma related to Hydrochlorothiazide: Hydrochlorothiazide, a sulfonamide, can cause an idiosyncratic reaction, resulting in choroidal effusion, acute transient myopia and/or acute angle-closure glaucoma. Symptoms include acute onset of decreased visual acuity, blurred vision or ocular pain and typically occur within hours to weeks of drug initiation. Untreated acute angle-closure glaucoma can lead to permanent vision loss.
The primary treatment is to discontinue Auro-Candesartan HCT as rapidly as possible. Prompt medical or surgical treatments may need to be considered if the intraocular pressure remains uncontrolled. Risk factors for developing acute angle-closure glaucoma may include a history of sulfonamide or penicillin allergy.
Peri-Operative Considerations
Thiazides may increase the responsiveness to tubocurarine.
Renal
Renal Impairment: As a consequence of inhibiting the renin-angiotensin-aldosterone system (RAAS), changes in renal function have been seen in susceptible individuals. In patients whose renal function may depend on the activity of the RAAS, such as patients with bilateral renal artery stenosis, unilateral renal artery stenosis to a solitary kidney, or severe congestive heart failure, treatment with agents that inhibit this system has been associated with oliguria, progressive azotemia, and rarely, acute renal failure and/or death. In susceptible patients, concomitant diuretic use may further increase risk.
The use of ARBs, including the candesartan cilexetil component of Auro-Candesartan HCT, or ACEIs with aliskiren-containing drugs is contraindicated in patients with moderate to severe renal impairment (GFR < 60 mL/min/1.73m2) (see 2 CONTRAINDICATIONS and 9.4 Drug-Drug Interactions).
Use of candesartan cilexetil should include appropriate assessment of renal function. Thiazides should be used with caution.
In patients with mild to moderate renal impairment (i.e., creatinine clearance between 30-80 mL/min/1.73m2 BSA), a dose titration is recommended (see Renal Impairment).
Because of the hydrochlorothiazide component, Auro-Candesartan HCT is contraindicated in patients with severe renal impairment (creatinine clearance < 30 mL/min/1.73 m2 BSA) (see 2 CONTRAINDICATIONS and Renal Impairment).
Renal Transplantation: There is limited experience regarding the administration of candesartan in patients with renal transplant.
Azotemia: Azotemia may be precipitated or increased by hydrochlorothiazide. Cumulative effects of the drug may develop in patients with impaired renal function. If increasing azotemia and oliguria occur during treatment of severe progressive renal disease, the diuretic should be discontinued.
Respiratory
Acute respiratory toxicity: Severe cases of acute respiratory toxicity, including acute respiratory distress syndrome (ARDS), have been reported after taking hydrochlorothiazide. Pulmonary edema typically develops within minutes to hours after hydrochlorothiazide intake. At the onset, symptoms include dyspnea, fever, pulmonary deterioration, and hypotension. If diagnosis of ARDS is suspected, Auro-Candesartan HCT should be withdrawn, and appropriate treatment given. Hydrochlorothiazide should not be administered to patients who previously experienced ARDS following hydrochlorothiazide intake.
Skin
Photosensitivity: Photosensitivity reactions have been reported with the use of thiazide diuretics.
If photosensitivity reactions occur during treatment with hydrochlorothiazide-containing drugs, treatment should be stopped.
7.1 Special Populations
7.1.1 Pregnant Women
Auro-Candesartan HCT is contraindicated during pregnancy (see 2 CONTRAINDICATIONS). Drugs that act directly on the RAAS can cause fetal and neonatal morbidity and death when administered to pregnant women. When pregnancy is detected, Auro-Candesartan HCT should be discontinued as soon as possible.
Epidemiological evidence regarding the risk of teratogenicity following exposure to ACEIs during the first trimester of pregnancy has not been conclusive; however, a small increase in risk cannot be excluded. Given the current evidence available on the risk with ARBs, similar risks may exist for this class of drugs. Patients planning pregnancy should be changed to alternative anti-hypertensive treatments which have an established safety profile for use in pregnancy. When pregnancy is diagnosed, treatment with ARBs should be stopped immediately, and, if appropriate, alternative therapy should be started.
The use of ARBs during the second and third trimesters is known to induce human fetotoxicity (decreased renal function, oligohydramnios, skull ossification retardation) and neonatal toxicity (renal failure, hypotension, hyperkalemia).
There is limited experience with hydrochlorothiazide during pregnancy, especially during the first trimester. Thiazides cross the placental barrier and appear in cord blood. The routine use of diuretics in otherwise healthy pregnant women is not recommended. Based on the pharmacological mechanism of action of hydrochlorothiazide, its use during pregnancy may compromise feto placental perfusion and may cause fetal and neonatal effects like icterus, disturbance of electrolyte balance, thrombocytopenia and possibly other adverse experiences which have occurred in the adult. Diuretics do not prevent development of toxemia of pregnancy and there is no satisfactory evidence that they are useful in the treatment of toxemia.
Animal Data: Oral doses ≥ 10 mg candesartan cilexetil/kg/day administered to pregnant rats during late gestation and continued through lactation were associated with reduced survival and an increased incidence of hydronephrosis in the offspring. Candesartan cilexetil given to pregnant rabbits at an oral dose of 3 mg/kg/day caused maternal toxicity (decreased body weight and death) but, in surviving dams, had no adverse effects on fetal survival, fetal weight, or external, visceral, or skeletal development. No maternal toxicity or adverse effects on fetal development were observed when oral doses ≤1000 mg candesartan cilexetil/kg/day were administered to pregnant mice.
7.1.2 Breast-feeding
It is not known whether candesartan is excreted in human milk, but significant levels have been found in the milk of lactating rats. Thiazides appear in human milk. Because many drugs are excreted in human milk, and because of their potential for adversely affecting the nursing infant, a decision should be made whether to discontinue nursing or to discontinue the drug, taking into account the importance of the drug to the mother (see 2 CONTRAINDICATIONS).
7.1.3 Pediatrics
Pediatrics (< 18 years of age): No data are available to Health Canada; therefore, Health Canada has not authorized an indication for pediatric use.
Auro-Candesartan HCT is contraindicated in children aged < 1 year (see 2 CONTRAINDICATIONS).
In utero exposure: Infants with a history of in utero exposure to ARBs should be closely observed for hypotension, oliguria, and hyperkalemia. If oliguria occurs, attention should be directed toward support of blood pressure and renal perfusion. Exchange transfusion or dialysis may be required as a means of reversing hypotension and/or substituting for impaired renal function; however, limited experience with those procedures has not been associated with significant clinical benefit. Candesartan cilexetil is not removed from plasma by dialysis.
7.1.4 Geriatrics
Geriatrics (> 65 years of age): No overall differences in safety or effectiveness were observed between the younger and elderly patients but greater sensitivity of some older patients cannot be ruled out and appropriate caution is recommended.
8 ADVERSE REACTIONS
8.1 Adverse Reaction Overview
Candesartan cilexetil/hydrochlorothiazide has been evaluated for safety in over 2500 patients treated for hypertension, including more than 700 treated for six months or more, and 500 for about one year or more. In placebo controlled double blind studies to support candesartan cilexetil/hydrochlorothiazide 16 mg / 12. 5 mg, candesartan cilexetil/hydrochlorothiazide combination was administered to 1025 hypertensive patients. Approximately 600 patients received candesartan cilexetil/hydrochlorothiazide 16 mg / 12.5 mg. The overall exposure amounts to 977 patient-years. Safety of the higher strength combinations of candesartan cilexetil/hydrochlorothiazide, 32 mg / 12.5 mg and 32 mg / 25 mg, has also been evaluated. In controlled clinical studies 718 patients were treated with candesartan/hydrochlorothiazide 32 mg / 12.5 mg and 1155 patients were treated with 32 mg / 25 mg; the total exposure in patient years in these studies was 107.8 and 175.3 years, respectively.
In general, adverse events were mild and transient in controlled clinical studies with various doses of candesartan cilexetil/hydrochlorothiazide (candesartan cilexetil up to 32 mg and hydrochlorothiazide up to 25 mg). The overall incidence of adverse events showed no association with age or gender.
In controlled clinical studies, discontinuation due to adverse events occurred in 2.3-3.3% and 2.7-4.3% of patients treated with candesartan cilexetil/hydrochlorothiazide and placebo, respectively. In studies to support the 16 mg / 12.5 mg strength, the incidence of serious adverse events observed with candesartan cilexetil/hydrochlorothiazide was 2.7% (71 out of 2582 patients). The incidence of serious adverse events was lower in the candesartan cilexetil/hydrochlorothiazide 32 mg / 12.5 mg and 32 mg / 25 mg dosage groups with the highest frequency of 0.8% (5 out of 664 patients) observed in the 32 mg / 25 mg group.
8.2 Clinical Trial Adverse Reactions
Clinical trials are conducted under very specific conditions. The adverse reaction rates observed in the clinical trials; therefore, may not reflect the rates observed in practice and should not be compared to the rates in the clinical trials of another drug. Adverse reaction information from clinical trials may be useful in identifying and approximating rates of adverse drug reactions in real-world use.
In the double blind placebo controlled studies to support candesartan cilexetil/ hydrochlorothiazide 16 mg / 12.5 mg, the overall incidence of adverse events showed no association with age or gender. In these studies the following adverse events reported with candesartan cilexetil/hydrochlorothiazide occurred in ≥ 1% of patients, regardless of drug relationship (see Table 2).
Table 2 Adverse events reported with candesartan cilexetil/hydrochlorothiazide in ≥ 1% of patients regardless of causality in studies supporting the 16 mg / 12.5 mg strength
Candesartan cilexetil/ hydrochloro -thiazide (n=1 025) | Candesartan cilexetil (n=749) | Hydrochloro -thiazide (n=603) | Placebo (n=526) | |||||
|---|---|---|---|---|---|---|---|---|
| % | % | % | % | |||||
| Cardiac Disorders | ||||||||
| tachycardia | 1.3 | 0.9 | 1.2 | 0.8 | ||||
Candesartan cilexetil/ hydrochloro -thiazide (n=1 025) | Candesartan cilexetil (n=749) | Hydrochloro -thiazide (n=603) | Placebo (n=526) | |||||
|---|---|---|---|---|---|---|---|---|
| % | % | % | % | |||||
| ECG abnormal | 1.2 | 1.2 | 0.3 | 0.8 | ||||
| edema peripheral | 1.1 | 1.6 | 2.2 | 1.3 | ||||
| chest pain | 1.0 | 0.7 | 1.0 | 0.6 | ||||
| Gastrointestinal Disorders | ||||||||
| nausea | 1.5 | 0.9 | 1.2 | 0.6 | ||||
| diarrhea | 1.1 | 0.7 | 0.5 | 1.3 | ||||
| gastroenteritis | 1.0 | 0.5 | 1.0 | 0.4 | ||||
| General disorders | ||||||||
| fatigue | 1.4 | 1.2 | 1.7 | 1.0 | ||||
| abdominal pain | 1.3 | 1.7 | 0.7 | 1.1 | ||||
| Infections and Infestations | ||||||||
| urinary tract infection | 1.6 | 1.3 | 1.8 | 1.0 | ||||
| Metabolism and Nutrition Disorders | ||||||||
| hyperuricemia | 1.1 | 0.7 | 0.8 | 0.4 | ||||
| hyperglycemia | 1.0 | 0.9 | 0.5 | 0.2 | ||||
| Musculoskeletal, connective tissue and bone disorders | ||||||||
| back pain | 3.8 | 5.5 | 5.1 | 3.0 | ||||
| arthralgia | 1.5 | 1.3 | 1.3 | 0.8 | ||||
| Nervous System Disorders | ||||||||
| headache | 4.3 | 7.6 | 7.6 | 7.0 | ||||
| dizziness | 3.1 | 3.9 | 2.0 | 1.5 | ||||
| inflicted injury | 2.0 | 2.0 | 3.0 | 1.9 | ||||
| Respiratory, Thoracic and Mediastinal Disorders | ||||||||
| upper respiratory tract infection | 3.7 | 5.1 | 5.6 | 1.9 | ||||
| influenza-like symptoms | 2.8 | 2.3 | 3.0 | 2.9 | ||||
| sinusitis | 2.3 | 2.9 | 3.5 | 1.9 | ||||
| bronchitis | 2.1 | 2.8 | 2.5 | 2.5 | ||||
| pharyngitis | 1.4 | 0.9 | 1.0 | 1.7 | ||||
| rhinitis | 1.2 | 1.5 | 1.2 | 0.4 | ||||
| cough | 0.9 | 2.3 | 1.7 | 1.0 | ||||
In double blind, controlled studies with candesartan cilexetil/hydrochlorothiazide 32 mg / 12.5 mg, and 32 mg / 25 mg the following adverse events reported with candesartan cilexetil/hydrochlorothiazide occurred in ≥ 1% of patients, regardless of drug relationship (see Table 3).
Table 3 Adverse events reported with candesartan cilexetil/hydrochlorothiazide 32 mg / 12.5 mg and 32 mg / 25 mg in ≥ 1% of patients regardless of causality
Candesartan cilexetil/ hydrochlorothiazide (n=1 873) | Candesartan cilexetil (n=1188) | Hydrochloro-thiazide (n=540) | Placebo (n=163) | |||||||||
|---|---|---|---|---|---|---|---|---|---|---|---|---|
32 mg / 12.5 mg (n= 718) | 32 mg / 25 mg (n= 1155) | |||||||||||
| % | % | % | % | % | ||||||||
| Gastrointestinal Disorders | ||||||||||||
| diarrhea | 1.1 | 0.4 | 0.7 | 0.4 | 1.8 | |||||||
| General disorders | ||||||||||||
| fatigue | 1.1 | 0.9 | 0.8 | 0.4 | 2.5 | |||||||
| Metabolism and Nutrition Disorders | ||||||||||||
| dyslipidemia | 3.3 | 2.5 | 1.9 | 0.4 | 0 | |||||||
| Musculoskeletal, connective tissue and bone disorders | ||||||||||||
| back pain | 2.4 | 1.6 | 1.1 | 0.6 | 2.5 | |||||||
| arthralgia | 0.6 | 1.1 | 0.6 | 1.1 | 1.8 | |||||||
| Nervous System Disorders | ||||||||||||
| dizziness | 2.5 | 2.9 | 1.3 | 2.4 | 0.6 | |||||||
| headache | 2.4 | 2.0 | 5.1 | 7.6 | 7.4 | |||||||
| Respiratory, Thoracic and Mediastinal Disorders | ||||||||||||
| cough | 1.4 | 0.7 | 0.6 | 1.3 | 1.2 | |||||||
| nasopharyngitis | 1.3 | 1.4 | 1.0 | 0.6 | 0 | |||||||
| upper respiratory tract infection | 1.3 | 0.3 | 1.7 | 3.5 | 5.5 | |||||||
| bronchitis | 1.1 | 0.9 | 1.0 | 1.3 | 1.2 | |||||||
8.3 Less Common Clinical Trial Adverse Reactions
Candesartan cilexetil
The following adverse events were reported at an incidence of <1% in controlled clinical trials (in more than one patient, with higher frequency than placebo):
- Blood: anemia, epistaxis.
- Body as a Whole: allergy, asthenia, pain, syncope.
- Cardiovascular: angina pectoris, circulatory failure, flushing, hypotension, myocardial infarction, peripheral ischemia, thrombophlebitis.
- Central and Peripheral Nervous System: hypertonia, hypoesthesia, paresthesia, vertigo.
- Gastrointestinal: constipation, dyspepsia, dry mouth, toothache.
- Hearing: tinnitus.
- Metabolic and Nutritional: diabetes mellitus, hyperkalemia, hyponatremia.
- Musculoskeletal: arthritis, arthropathy, myalgia, myopathy, skeletal pain, tendon disorder.
- Psychiatric: depression, impotence, neurosis.
- Reproductive: menopausal symptoms.
- Resistance Mechanism: otitis.
- Respiratory: laryngitis.
- Skin: eczema, pruritus, rash, skin disorder, sweating, (rarely) urticaria.
- Urinary: abnormal urine, cystitis.
- Vision: conjunctivitis.
There was no clear indication of dose-response relationship for any of the most common adverse events.
8.4 Abnormal Laboratory Findings: Hematologic, Clinical Chemistry and Other Quantitative Data
In controlled clinical trials, clinically important changes in standard laboratory parameters were rarely associated with administration of candesartan cilexetil/hydrochlorothiazide.
Blood glucose: in controlled clinical trials, elevations of blood glucose occurred in 1.0% of patients treated with candesartan cilexetil/hydrochlorothiazide compared to 0.2% of patients receiving placebo.
Creatinine, Urea: An increase in creatinine and urea has been observed with candesartan cilexetil/hydrochlorothiazide.
Hemoglobin and Hematocrit: small decreases in hemoglobin were observed in patients treated with candesartan cilexetil/hydrochlorothiazide but were rarely of clinical importance. Values of hemoglobin below the predefined critical limit were recorded in 0.9% of patients in controlled clinical trials with candesartan cilexetil/hydrochlorothiazide.
Hyperuricemia: increases in serum uric acid were found in 1.1% of patients treated with candesartan cilexetil/hydrochlorothiazide and 0.4% of patients treated with placebo.
Liver Function Tests: in controlled clinical trials, elevations of ALT (> 3 times the upper limit of normal) occurred in 0.9% of patients treated with candesartan cilexetil/hydrochlorothiazide compared to 0% of patients receiving placebo. Minor increases in serum AST have been observed in single patients receiving candesartan cilexetil/hydrochlorothiazide.
Serum Potassium, Sodium: a small decrease (mean decrease of 0.1 mmol/L) in serum potassium was observed in patients treated with candesartan cilexetil/hydrochlorothiazide but was rarely of clinical importance. Values of serum potassium below the predefined lower critical limit were recorded in 0.6% of patients in controlled clinical trials with candesartan cilexetil/hydrochlorothiazide. An increase in serum potassium has rarely been observed with candesartan cilexetil/hydrochlorothiazide. A decrease in sodium has been observed with candesartan cilexetil/hydrochlorothiazide.
8.5 Post-Market Adverse Reactions
Candesartan cilexetil
Angioedema, (involving swelling of the face, lips and/or tongue) has been reported rarely in patients treated with candesartan cilexetil.
In other post-marketing experience, renal impairment, including renal failure in susceptible patients, has been observed (see Renal Impairment).
Very rare cases of abnormal hepatic function or hepatitis have also been reported.
Other adverse events reported for candesartan cilexetil where a causal relationship could not be established include very rare cases of leukopenia, neutropenia and agranulocytosis.
Cases of muscle pain, muscle weakness, myositis and rhabdomyolysis have been reported in patients receiving angiotensin II receptor blockers.
Hydrochlorothiazide
Potentially serious clinical adverse events have been reported to occur with hydrochlorothiazide, such as:
Blood and lymphatic system disorders: aplastic anemia; hemolytic anemia; leukopenia;
neutropenia/agranulocytosis; thrombocytopenia.
Eye Disorders: acute angle-closure glaucoma; acute myopia; choroidal effusion.
Endocrine and Metabolism: hypokalemia.
Gastrointestinal disorders: pancreatitis.
Hepatobiliary disorders: jaundice (intrahepatic cholestatic jaundice).
Immune system disorders: anaphylactic reactions; photosensitivity reactions.
Musculoskeletal and connective tissue disorders: cutaneous lupus erythematosus; systemic lupus erythematosus.
Respiratory, thoracic and mediastinal disorders: respiratory distress (including pneumonitis, pulmonary edema, and acute respiratory distress syndrome) (see Respiratory).
Renal and urinary disorders: interstitial nephritis; renal dysfunction. Skin and subcutaneous tissue disorders: toxic epidermal necrolysis. Vascular disorders: necrotising angitis (vasculitis).
Non-melanoma skin cancer: Some pharmacoepidemiological studies have suggested a higher risk of squamous cell carcinoma (SCC) and basal cell carcinoma (BCC) of the skin with increasing use of hydrochlorothiazide. A systematic review and meta-analysis undertaken by Health Canada suggested that, with important uncertainty, the use of hydrochlorothiazide for several years (>3 years) could lead to:
122 additional cases (95% CI, from 112 to 133 additional cases) of SCC per 1000 treated
- patients compared with non-use of hydrochlorothiazide (meta-analysis of 3 observational studies);
- 31 additional cases (95% CI, from 24 to 37 additional cases) of BCC per 1000 treated patients compared with non-use of hydrochlorothiazide (meta-analysis of 2 observational studies).
9 DRUG INTERACTIONS
9.1 Serious Drug Interactions
Serious Drug Interactions
|
|---|
9.2 Drug Interactions Overview
In vitro studies indicate that cytochrome P450 isoenzyme CYP 2C9 is involved in the biotransformation of candesartan to its inactive metabolite. Based on in vitro data, no interaction would be expected to occur in vivo with drugs whose metabolism is dependent upon cytochrome P450 isoenzymes CYP1A2, CYP2A6, CYP2C9, CYP2C19, CYP2D6, CYP2E1 or CYP3A4.
9.3 Drug-Behavioural Interactions
Consumption of alcohol while using Auro-Candesartan HCT may potentiate the risk of orthostatic hypotension (see 9.4 Drug-Drug Interactions)
9.4 Drug-Drug Interactions
The drugs listed in this table are based on either drug interaction case reports or studies, or potential interactions due to the expected magnitude and seriousness of the interaction (i.e., those identified as contraindicated).
Table 4 Established or Potential Drug-Drug Interactions
| Proper Name | Source of Evidence | Effect | Clinical Comment |
|---|---|---|---|
| Agents Increasing Serum Potassium | T | Candesartan cilexetil decreases the production of aldosterone. | Potassium-sparing diuretics, potassium supplements or other drugs that may increase serum potassium levels (e.g. heparin, co-trimoxazole) should be given |
| Proper Name | Source of Evidence | Effect | Clinical Comment | |
|---|---|---|---|---|
only for documented hypokalemia and with frequent monitoring of serum potassium. Potassium-containing salt substitutes should also be used with caution. Concomitant thiazide diuretic use, or switching to Auro-Candesartan HCT may attenuate any effect that candesartan cilexetil may have on serum potassium. | ||||
| Alcohol, barbiturates or narcotics | C | Potentiation of orthostatic hypotension may occur. | Avoid alcohol, barbiturates or narcotics, especially with initiation of therapy. | |
| Amantadine | T | Co-administration of thiazide diuretics may increase the risk of adverse effects caused by amantadine. | Monitor the patient closely and adjust the dosage of either medication as required. | |
| Amphotericin B | T | Amphotericin B increases the risk of hypokalemia induced by thiazide diuretics. | Monitor serum potassium level. | |
| Anti-cholinergic agents (e.g., atropine, biperiden, domperidone and metoclopramide) | CT,T | Bioavailability of thiazide diuretics may be increased by anticholinergic agents due to a decrease in gastrointestinal motility and gastric emptying. Conversely, prokinetic drugs may decrease the bioavailability of thiazide diuretics. | Dose adjustment of Auro-Candesartan HCT may be required. | |
Antidiabetic agents (e.g. insulin or oral hypoglycemic agents) | CT | Thiazide-induced hyperglycemia may compromise blood sugar control. Depletion of serum potassium augments glucose intolerance. | Monitor glycemic control, supplement potassium if necessary, to maintain appropriate serum potassium levels, and adjust diabetes medications as required. | |
| Antihypertensive | CT | Hydrochlorothiazide may | Dose adjustments of other | |
| Proper Name | Source of Evidence | Effect | Clinical Comment |
|---|---|---|---|
| drugs | potentiate the action of other antihypertensive drugs (e.g. guanethidine, methyldopa, beta- blockers, vasodilators, calcium channel blockers, ACEI, ARB, and direct renin inhibitors). | concomitantly taken antihypertensive drugs may be required. | |
| Antineoplastic drugs, including cyclophosphamide and methotrexate | C | Concomitant use of thiazide diuretics may reduce renal excretion of cytotoxic agents and enhance their myelosuppressive effects. | Hematologic status should be closely monitored in patients receiving this combination. Dose adjustment of cytotoxic agents may be required. |
Bile acid sequestrants e.g. cholestyramine | CT | Bile acid sequestrants bind thiazide diuretics in the gut and impair gastrointestinal absorption by 43-85%. Administration of thiazide 4 hours after a bile acid sequestrant reduced absorption of hydrochlorothiazide by 30-35%. | Give Auro-Candesartan HCT 2-4 hours before or 6 hours after the bile acid sequestrant. Maintain a consistent sequence of administration. Monitor blood pressure, and increase dose of Auro-Candesartan HCT, if necessary. |
| Calcium and Vitamin D supplements | C | Administration of thiazide with vitamin D, or with calcium salts may potentiate the rise in serum calcium. Thiazides decrease renal excretion of calcium and increase calcium release from bone. | Monitor serum calcium, especially with concomitant use of high doses of calcium supplements. Dose reduction or withdrawal of calcium and/or vitamin D supplements may be necessary. |
| Carbamazepine | C | Carbamazepine may cause clinically significant hyponatremia. Concomitant use with thiazide diuretics may potentiate hyponatremia. | Monitor serum sodium levels. Use with caution. |
| Corticosteroids, and | T | Intensified electrolyte | Monitor serum potassium and |
| Proper Name | Source of Evidence | Effect | Clinical Comment |
|---|---|---|---|
| adrenocorticotropic hormone (ACTH) | depletion, particularly hypokalemia, may occur when given concomitantly with thiazide diuretics. | adjust medications, as required. | |
| Cyclosporine | T | May increase the risk of hyperuricemia and gout type complications. | Serum uric acid levels should be closely monitored and medications adjusted, as required. |
| Diazoxide | C | Co-administration of thiazide diuretics enhances the hyperglycemic effect of diazoxide. | Blood glucose levels should be monitored and dose adjustment of insulin or antidiabetics may be required in diabetic patients. |
| Digoxin | CT | Combination treatment with candesartan cilexetil and digoxin in healthy volunteers had no effect on AUC or Cmax values for digoxin compared to digoxin alone. Similarly, combination treatment had no effect on AUC or Cmax values for candesartan compared to candesartan cilexetil alone. Thiazide-induced electrolyte disturbances, i.e. hypokalemia, hypomagnesemia, increase the risk of digoxin toxicity, which may lead to fatal arrhythmic events. | Concomitant administration of Auro-Candesartan HCT and digoxin requires caution. Monitor electrolytes and digoxin levels closely. Supplement potassium or adjust doses of digoxin or Auro-Candesartan HCT, as required. |
| Diuretics | CT | Patients on diuretics, and especially those in whom diuretic therapy was recently instituted, may occasionally experience an excessive reduction of blood pressure after initiation of therapy with candesartan cilexetil. | The possibility of symptomatic hypotension with the use of candesartan cilexetil can be minimized by discontinuing the diuretic prior to initiation of treatment and/or lowering the initial dose of candesartan cilexetil (see Hypotension and 4 DOSAGE AND ADMINISTRATION). |
| Proper Name | Source of Evidence | Effect | Clinical Comment | |
|---|---|---|---|---|
| No drug interactions of clinical significance have been identified with thiazide diuretics. When Auro-Candesartan HCT is used, other diuretics are, as a rule, unnecessary. | ||||
| Dual blockade of the Renin- Angiotensin- System (RAS) with ARBs, ACEIs or aliskiren- containing drugs | CT | Clinical trial data have shown that dual blockade of the RAS through the combined use of ACE-inhibitors, angiotensin II receptor blockers or aliskiren is associated with a higher frequency of adverse events such as hypotension, hyperkalemia and decreased renal function (including acute renal failure) compared to the use of a single RAS- acting agent. | Dual blockade of the RAS with ARBs or ACEIs and aliskiren- containing drugs is contraindicated in patients with diabetes and/or renal impairment (see 2 CONTRAINDICATIONS). The combined use of ARBs, ACEIs or aliskiren-containing drugs is generally not recommended (see Dual blockade of the Renin- Angiotensin System (RAS)). | |
| Gout medications (allopurinol, uricosurics, xanthine oxidase inhibitors) | T, RCS | Thiazide-induced hyperuricemia may compromise control of gout by allopurinol and probenecid. The co- administration of hydrochlorothiazide and allopurinol may increase the incidence of hypersensitivity reactions to allopurinol. | Use of Auro-Candesartan HCT in patients with gout is contraindicated (see 2 CONTRAINDICATIONS). | |
| Lithium Salts | CT | As with other drugs which eliminate sodium, lithium clearance may be reduced. Lithium generally should not be given with diuretics. Diuretic agents reduce the renal clearance of lithium and add a high risk of lithium toxicity. | Concomitant use of Auro-Candesartan HCT with lithium is generally not recommended. If such use is deemed necessary, reduce lithium dose by 50% and monitor closely. Serum lithium levels should be monitored carefully if lithium salts are to be administered. | |
| Proper Name | Source of Evidence | Effect | Clinical Comment |
|---|---|---|---|
| Methyldopa | C | There have been reports in the literature of hemolytic anemia occurring with concomitant use of hydrochlorothiazide and methyldopa. | Monitor for symptoms of anemia. If anemia is confirmed, tests should be done for hemolysis. If hemolytic anemia is present, Auro-Candesartan HCT should be discontinued. |
| Nonsteroidal Anti- Inflammatory Drugs (NSAIDs) | CT | In some patients, the administration of an NSAID can reduce the diuretic, natriuretic, and antihypertensive effects of loop, potassium- sparing and thiazide diuretics. Attenuation of the antihypertensive effect may occur when simultaneously administering ARBs and NSAIDs (i.e. selective COX-2 inhibitors, acetylsalicylic acid and non-selective NSAIDs). As with ACE inhibitors, concomitant use of ARBs and NSAIDs may lead to an increased risk of worsening of renal function, including possible acute renal failure, and an increase in serum potassium, especially in patients with poor pre-existing renal function. | When Auro-Candesartan HCT and NSAIDs are used concomitantly, the patient should be observed closely to determine if the desired effect of the diuretic is obtained. The combination of ARBs and NSAIDs should be administered with caution, especially in older patients and in volume depleted patients. Patients should be adequately hydrated and consideration should be given to monitoring renal function after initiation of concomitant therapy and periodically thereafter. If combination use is necessary, monitor renal function, serum potassium, and blood pressure closely. Dose adjustments may be required. Patients with heart failure may be at particular risk. |
| Pressor Amines (e.g., norepinephrine) | T | In the presence of thiazide diuretics possible decreased response to pressor amines may be seen but not sufficient to preclude their use. | Monitor and consider dose adjustments if required. |
| Selective Serotonin | T,C | Concomitant use with thiazide diuretics may | Monitor serum sodium levels. Use with caution. |
| Proper Name | Source of Evidence | Effect | Clinical Comment | |
|---|---|---|---|---|
| Reuptake Inhibitors (SSRIs, e.g., citalopram, escitalopram, sertraline) | potentiate hyponatremia. | |||
| Skeletal muscle relaxants of the curare family, e.g., tubocurarine | C | Thiazide drugs may increase the responsiveness of some nondepolarizing skeletal muscle relaxants, such as curare derivatives. | ||
| Topiramate | CT | Additive hypokalemia. Possible thiazide- induced increase in topiramate serum concentrations. | Monitor serum potassium and topiramate levels. Use potassium supplements, or adjust topiramate dose as necessary. | |
| Warfarin | CT | When candesartan cilexetil was administered at 16 mg once daily under steady state conditions, no pharmacodynamic effect on prothrombin time was demonstrated in subjects stabilized on warfarin. | ||
| Other | CT | No significant drug interactions have been reported with glyburide, nifedipine or oral contraceptives co- administered with candesartan cilexetil to healthy volunteers. | ||
Legend: C= Case Study; RCS=Retrospective Cohort Study; CT= Clinical Trial; T= Theoretical
9.5 Drug-Food Interactions
Auro-Candesartan HCT may be taken with or without food (see 4 DOSAGE AND ADMINISTRATION).
9.6 Drug-Herb Interactions
Interactions with herbal products have not been established.
9.7 Drug-Laboratory Test Interactions
Interactions with laboratory tests have not been established.
10 CLINICAL PHARMACOLOGY
10.1 Mechanism of Action
Candesartan cilexetil/hydrochlorothiazide combines the actions of candesartan cilexetil, an angiotensin II AT1 receptor blocker, and that of a thiazide diuretic, hydrochlorothiazide.
Candesartan cilexetil
Candesartan cilexetil antagonizes the action of angiotensin II by blocking the angiotensin type one (AT1) receptor. Angiotensin II is the primary vasoactive hormone of the RAAS with effects that include vasoconstriction, stimulation of aldosterone secretion, and renal reabsorption of sodium.
Candesartan cilexetil, a prodrug, is rapidly converted to the active drug, candesartan, during absorption from the gastrointestinal tract.
Candesartan blocks the vasoconstrictor and aldosterone secreting effects of angiotensin II by selectively blocking the binding of angiotensin II to the AT1 receptor in many tissues, such as vascular smooth muscle and the adrenal gland. Its action is therefore independent of the pathways for angiotensin II synthesis. There are also AT2 receptors found in many tissues, but they play no known role in cardiovascular homeostasis to date. Candesartan has a much greater affinity (> 10,000-fold) for the AT1 receptor than for the AT2 receptor. The strong bond between candesartan and the AT1 receptor is a result of tight binding to and slow dissociation from the receptor.
Candesartan does not inhibit ACE, also known as kininase II, the enzyme that converts angiotensin I to angiotensin II and degrades bradykinin, nor does it bind to or block other hormone receptors or ion channels known to be important in cardiovascular regulation.
Hydrochlorothiazide
Hydrochlorothiazide is a diuretic and antihypertensive which interferes with the renal tubular mechanism of electrolyte reabsorption. It inhibits the active reabsorption of sodium, mainly in the distal kidney tubules, and promotes the excretion of sodium, chloride and water. The renal excretion of potassium and magnesium increases dose-dependently, while calcium is reabsorbed to a greater extent. While this compound is predominantly a saluretic agent, in vitro studies have shown that it has a carbonic anhydrase inhibitory action which seems to be relatively specific for the renal tubular mechanism. It does not appear to be concentrated in erythrocytes or the brain in sufficient amounts to influence the activity of carbonic anhydrase in those tissues.
Hydrochlorothiazide is useful in the treatment of hypertension. It may be used alone or as an adjunct to other antihypertensive drugs. Hydrochlorothiazide does not affect normal blood pressure.
10.2 Pharmacodynamics
Candesartan cilexetil
Candesartan inhibits the pressor effects of angiotensin II infusion in a dose-dependent manner.
After 1 week of once-daily dosing of 8 mg candesartan cilexetil, the pressor effect was inhibited by approximately 90% at peak (4-8 hours after dosing) with approximately 50% inhibition persisting at 24 hours. Plasma concentrations of angiotensin I, angiotensin II (AII), and plasma renin activity, increased in a dose-dependent manner after single and repeated administration of candesartan cilexetil to healthy subjects and hypertensive patients. A decrease in the plasma concentration of aldosterone was observed when 32 mg of candesartan cilexetil was administered to hypertensive patients.
Hydrochlorothiazide
Onset of the diuretic action following oral administration occurs in 2 hours and the peak action in about 4 hours. Diuretic activity lasts about 6 to 12 hours.
In Vitro and Animal Pharmacology: In an in vitro assay system, hydrochlorothiazide at 10-5 M did not affect the inhibition of binding of [125I]-labeled AII to the AII receptor by candesartan.
HCTZ at 10 mg/kg/day had no effect on blood pressure in conscious spontaneously hypertensive rats. HCTZ combined with 0.1 or 1 mg/kg of candesartan cilexetil, synergistically intensified the reduction in blood pressure induced by candesartan cilexetil.
10.3 Pharmacokinetics
Concomitant administration of candesartan cilexetil and hydrochlorothiazide has no clinically significant effect on the pharmacokinetics of either medicinal product.
Candesartan cilexetil
Absorption: Following oral administration of candesartan cilexetil as a tablet, the absolute bioavailability of candesartan is estimated to be approximately 15%. After tablet ingestion, the peak serum concentration (Cmax) is reached after 3-4 hours. Food does not affect the bioavailability of candesartan after candesartan cilexetil administration.
Distribution: The volume of distribution of candesartan is 0.13 L/kg. Candesartan is highly bound to plasma proteins (>99%) and does not penetrate red blood cells. The protein binding is constant at candesartan plasma concentrations well above the range achieved with recommended doses. In rats, it has been demonstrated that candesartan does cross the blood- brain barrier. It has also been demonstrated in rats that candesartan passes across the placental barrier and is distributed in the fetus.
Metabolism: Candesartan cilexetil is rapidly and completely bioactivated to candesartan by ester hydrolysis during absorption from the gastrointestinal tract. It undergoes minor hepatic metabolism by O-deethylation to an inactive metabolite. In vitro studies indicate that cytochrome P450 isoenzyme CYP 2C9 is involved in the biotransformation of candesartan to its inactive metabolite. Based on in vitro data, no interaction would be expected to occur in vivo with drugs whose metabolism is dependent upon cytochrome P450 isoenzymes CYP1A2, CYP2A6, CYP2C9, CYP2C19, CYP2D6, CYP2E1 or CYP3A4.
Elimination: Total plasma clearance of candesartan is 0.37 mL/min/kg, with a renal clearance of 0.19 mL/min/kg. Candesartan is mainly excreted unchanged in urine and feces (via bile). When candesartan cilexetil is administered orally, about 26% of the dose is excreted as candesartan in urine. Following an oral dose of 14C-labeled candesartan cilexetil, approximately 33% of radioactivity is recovered in urine and approximately 67% in feces. Following an intravenous (iv) dose of 14C-labeled candesartan, approximately 59% of radioactivity is recovered in urine and approximately 36% in feces. Biliary excretion contributes to the elimination of candesartan. The elimination half-life of candesartan is approximately 9 hours. After single and repeated administration, the pharmacokinetics of candesartan are linear, for oral doses ≤ 32 mg. Candesartan and its inactive metabolite do not accumulate in serum upon repeated once-daily dosing.
Hydrochlorothiazide
Absorption: Hydrochlorothiazide is rapidly absorbed from the gastrointestinal tract with an absolute bioavailability of approximately 70%. Concomitant food intake increases the absorption by approximately 15%.
Distribution: The bioavailability may decrease in patients with cardiac failure and pronounced edema. The plasma protein binding of hydrochlorothiazide is approximately 60%. The apparent volume of distribution is approximately 0.8 L/kg.
Elimination: Hydrochlorothiazide is not metabolized and is excreted almost entirely as unchanged drug by glomerular filtration and active tubular secretion. The terminal t½ of hydrochlorothiazide is approximately 8 hours. Approximately 70% of an oral dose is eliminated in the urine within 48 hours. The half-life of hydrochlorothiazide remains unchanged (8 hours) after administration of hydrochlorothiazide in combination with candesartan cilexetil. No accumulation of hydrochlorothiazide occurs after repeated doses of the combination compared to monotherapy.
The terminal t½ of hydrochlorothiazide is prolonged in patients with chronic heart failure.
Special Populations and Conditions
- Geriatrics: The plasma concentration of candesartan was higher in the elderly (≥ 65 years old) (Cmax was approximately 50% higher and AUC was approximately 80% higher) compared to younger subjects administered the same dose. The pharmacokinetics of candesartan were linear in the elderly, and candesartan and its inactive metabolite did not accumulate in the serum of these subjects upon repeated, once-daily administration.
The terminal t½ of hydrochlorothiazide is prolonged in the elderly.
- Sex: No gender-related differences in the pharmacokinetics of candesartan have been observed.
- Pregnancy and Breast-feeding: Hydrochlorothiazide crosses the placental but not the blood-brain barrier and is excreted in breast milk.
Hepatic Insufficiency
Mild to moderate hepatic impairment: There was an increase in the AUC of candesartan of approximately 20%. There was no drug accumulation in plasma in these patients.
Moderate to severe hepatic impairment: Cmax and AUC increased up to 5x in a very small group administered a single dose of 16 mg candesartan (see 2 CONTRAINDICATIONS and Hepatic Impairment).
Renal Insufficiency
The terminal t½ of hydrochlorothiazide is prolonged in patients with renal failure.
Mild to moderate renal impairment (Clcreat 31-60 mL/min/1.73m2): Cmax and AUC of candesartan increased by 40-60% and 50-90%, respectively, but t½ was not altered, compared to patients with normal renal function (Clcreat > 60 mL/min/1.73m2) during repeated dosing. There was no drug accumulation in plasma.
Severe renal impairment (Clcreat 15-30 mL/min/1.73m2): The increases in Cmax and AUC were 40-60% and 110%, respectively. The terminal t½ of candesartan was approximately 2x in patients with severe renal impairment, and these changes resulted in some accumulation in plasma.
Patients undergoing hemodialysis: The pharmacokinetics of candesartan were similar to those in patients with severe renal impairment (see 2 CONTRAINDICATIONS and Renal Impairment).
11 STORAGE, STABILITY AND DISPOSAL
Store at room temperature 15-30°C. Protect from moisture.
12 SPECIAL HANDLING INSTRUCTIONS
Not applicable.
PART II: SCIENTIFIC INFORMATION
13 PHARMACEUTICAL INFORMATION
Drug Substance
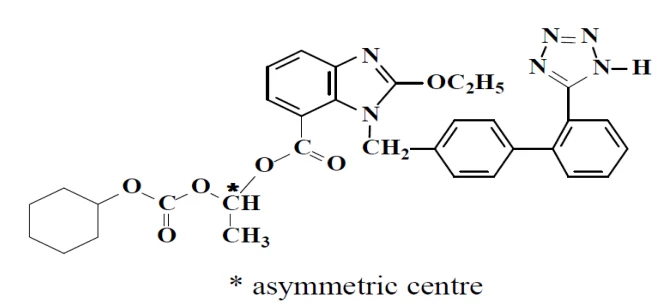
Proper name: candesartan cilexetil
+
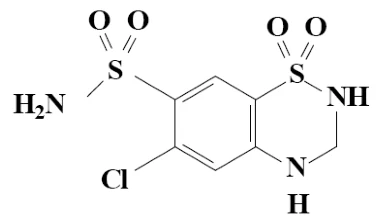
hydrochlorothiazide
Chemical name: (±)-1-[[(Cyclohexyloxy)carbonyl]oxy)ethyl-2-ethoxy-1-[[2'-(1H-tetrazol-5-yl) (1,1’-biphenyl)-4-yl] methyl]-1H-benzimidazole-7-carboxylate
+
6-chloro-3,4-dihydro-2H-1,2,4-benzothiadiazine-7-sulphonamide 1,1-dioxide
Molecular formula and molecular mass: C33H34N6O6 ; 610.67 g/mol
+
C7H8ClN3O4S2 ; 297.7 g/mol
Structural formula:
Physicochemical properties:
Description:
Candesartan cilexetil is a white or almost white powder.
Candesartan cilexetil is practically insoluble in water, freely soluble in methylene chloride and slightly soluble in anhydrous ethanol.
Hydrochlorothiazide is a white, or almost white, crystalline powder.
Hydrochlorothiazide is very slightly soluble in water, soluble in acetone, and sparingly soluble in alcohol. It dissolves in dilute solutions of alkali hydroxides.
14 CLINICAL TRIALS
14.1 Clinical Trials by Indication
Essential Hypertension
The details of the trial designs and study demographics for the studies on which the original indication was authorized are not available.
Candesartan cilexetil: In hypertension, candesartan cilexetil causes a dose-dependent reduction in arterial blood pressure (BP). Systemic peripheral resistance is decreased, while heart rate, stroke volume and cardiac output are not significantly affected. No first-dose hypotension was observed during controlled clinical trials with candesartan cilexetil.
Most of the antihypertensive effect was seen within 2 weeks of initial dosing, and the full effect in 4 weeks. With once-daily dosing, BP effect was maintained over 24 hours, with trough to peak ratios of BP effect generally > 80%. Candesartan cilexetil had an additional BP lowering effect when added to hydrochlorothiazide.
The antihypertensive effect was similar in men and women and in patients < 65 and ≥ 65 years. Candesartan was effective in reducing BP regardless of race, although the effect was somewhat less in Black patients (usually a low-renin population) than in Caucasian patients.
In long-term studies of ≤ 1 year, the antihypertensive effectiveness of candesartan cilexetil was maintained and there was no rebound after abrupt withdrawal.
Candesartan cilexetil also reduces urinary albumin excretion in patients with type II diabetes mellitus, hypertension, and microalbuminuria. In a 12-week study of 161 mildly hypertensive patients with type II diabetes mellitus, candesartan cilexetil 8-16 mg had no effect on mean HbA1c.
Comparative Effects: The antihypertensive efficacy of candesartan cilexetil and losartan potassium have been compared at their approved once daily maximum doses, 32 mg and 100 mg, respectively, in patients with mild to moderate essential hypertension. Candesartan cilexetil lowered systolic and diastolic blood pressure by 2 to 3 mm Hg on average more than losartan potassium when measured at the time of either peak or trough effect. Both agents were well tolerated.
Candesartan cilexetil/hydrochlorothiazide: Candesartan cilexetil and hydrochlorothiazide have additive antihypertensive effects. After administration of a single dose of candesartan cilexetil/hydrochlorothiazide in hypertensive patients, onset of the antihypertensive effect generally occurs within 2 hours. With continuous treatment, most of the reduction in blood pressure is attained within four weeks and is sustained during long-term treatment. Candesartan cilexetil/hydrochlorothiazide given once daily provides effective and smooth dose-dependent blood pressure reduction over 24 hours, with little difference between maximum and trough effects during the dosing interval and without reflex increase in heart rate. There is no indication of serious or exaggerated first dose hypotension or rebound effect after cessation of treatment.
Randomized placebo controlled studies with the combination of candesartan cilexetil and hydrochlorothiazide 32 mg / 12.5 mg or 32 mg / 25 mg once daily demonstrated a dose- dependent blood pressure lowering effect of candesartan cilexetil/hydrochlorothiazide. The combination produced a statistically significant effect larger than candesartan cilexetil or hydrochlorothiazide monotherapy. The proportion of patients with controlled blood pressure was larger and the effect of the combination was dose-related.
Candesartan cilexetil/hydrochlorothiazide is similarly effective in patients irrespective of age and gender.
14.2 Comparative Bioavailability Studies
A double blind, randomized, two-treatment, two-sequence, two-period, crossover, single-dose comparative oral bioavailability study of Auro-Candesartan HCT (Candesartan Cilexetil and Hydrochlorothiazide) Tablets, 32 mg/12.5 mg (Test) of Aurobindo Pharma Limited, India manufactured for Auro Pharma Inc., and Atacand® Plus (Candesartan Cilexetil and Hydrochlorothiazide) Tablets, 32 mg/12.5 mg (Reference) of AstraZeneca Canada Inc. was conducted in 41 healthy, adult, male subjects under fasting conditions.
Summary Table of the Comparative Bio-availability Data
Candesartan (1 X 32 mg candesartan cilexetil/12.5 mg hydrochlorothiazide) From measured data Geometric Mean Arithmetic Mean (CV %) | ||||
| Parameter | Test* | Reference † | % Ratio of Geometric Means | 90% Confidence Interval |
AUC0→t (hr.ng/mL) | 2808.8 2904.5 (26.9) | 3036.9 3270.9 (36.8) | 92.5 | 85.8-99.7 |
AUC0→∞ (hr.ng/mL) | 2911.9 3010.1 (26.8) | 3124.5 3369.6 (37.2) | 93.2 | 86.2-100.8 |
| Cmax (ng/mL) | 250.8 262.5 (30.4) | 280.8 298.8 (33.9) | 89.3 | 82.1-97.1 |
| Tmax§ (h) | 4.5 (2.3-6.0) | 4.0 (2.0-6.0) | ||
| T½$ (h) | 9.7 (39.4) | 9.1 (31.4) | ||
* Auro-Candesartan HCT (Candesartan Cilexetil and Hydrochlorothiazide) Tablets, 32 mg/12.5 mg by Auro Pharma Inc.
† ATACAND® PLUS (Candesartan Cilexetil and Hydrochlorothiazide) Tablets, 32 mg/12.5 mg manufactured by AstraZeneca Canada Inc., Canada were purchased in Canada.
§ Expressed as Median (Range) only.
$ Expressed as arithmetic mean (CV%) only.
Summary Table of the Comparative Bio-availability Data
Hydrochlorothiazide (1 X 32 mg candesartan cilexetil/12.5 mg hydrochlorothiazide) From measured data Geometric Mean Arithmetic Mean (CV %) | ||||
| Parameter | Test* | Reference † | % Ratio of Geometric Means | 90% Confidence Interval |
AUC0→t (hr.ng/mL) | 662.3 687.6 (26.6) | 664.2 696.0 (28.6) | 99.7 | 95.2-104.5 |
AUC0→∞ (hr.ng/mL) | 703.5 726.6 (25.2) | 698.6 725.2 (26.2) | 100.7 | 96.5-105.1 |
| Cmax (ng/mL) | 93.1 96.7 (26.6) | 97.0 102.2 (33.6) | 96.1 | 90.1-102.4 |
| Tmax§ (h) | 2.0 (1.0-4.5) | 2.3 (1.0-4.5) | ||
| T½$ (h) | 8.7 (25.2) | 8.9 (20.6) | ||
* Auro-Candesartan HCT (Candesartan Cilexetil and Hydrochlorothiazide) Tablets, 32 mg/12.5 mg by Auro Pharma Inc.
† ATACAND® PLUS (Candesartan Cilexetil and Hydrochlorothiazide) Tablets, 32 mg/12.5 mg manufactured by AstraZeneca Canada Inc., Canada were purchased in Canada.
§ Expressed as Median (Range) only.
$ Expressed as arithmetic mean (CV%) only.
A double blind, randomized, two-treatment, two-sequence, two-period, crossover, single-dose comparative oral bioavailability study of Auro-Candesartan HCT (Candesartan Cilexetil and Hydrochlorothiazide) Tablets, 32 mg/25 mg (Test) of Aurobindo Pharma Limited, India manufactured for Auro Pharma Inc., and Atacand® Plus (Candesartan Cilexetil and Hydrochlorothiazide) Tablets, 32 mg/25 mg (Reference) of AstraZeneca Canada Inc. was conducted in 43 healthy, adult, male subjects under fasting conditions.
Summary Table of the Comparative Bio-availability Data
Candesartan (1 X 32 mg candesartan cilexetil/25 mg hydrochlorothiazide) From measured data Geometric Mean Arithmetic Mean (CV %) | ||||
| Parameter | Test* | Reference † | % Ratio of Geometric Means | 90% Confidence Interval |
AUC0→t (hr.ng/mL) | 2690.7 2831.0 (32.0) | 3014.5 3190.9 (34.1) | 89.3 | 81.5-97.7 |
AUC0→∞ (hr.ng/mL) | 2775.2 2910.7 (31.0) | 3084.5 3263.3 (33.9) | 90.0 | 82.3-98.4 |
| Cmax (ng/mL) | 233.1 249.7 (36.4) | 262.2 277.4 (34.8) | 88.9 | 80.6-98.0 |
| Tmax§ (h) | 4.5 (2.0-8.0) | 4.5 (2.0-8.0) | ||
| T½$ (h) | 9.2 (26.4) | 8.5 (19.6) | ||
* Auro-Candesartan HCT (Candesartan Cilexetil and Hydrochlorothiazide) Tablets, 32 mg/25 mg by Auro Pharma Inc.
† ATACAND® PLUS (Candesartan Cilexetil and Hydrochlorothiazide) Tablets, 32 mg/25 mg manufactured by AstraZeneca Canada Inc., Canada were purchased in Canada.
§ Expressed as Median (Range) only.
$ Expressed as arithmetic mean (CV%) only.
Summary Table of the Comparative Bio-availability Data
Hydrochlorothiazide (1 X 32 mg candesartan cilexetil/25 mg hydrochlorothiazide) From measured data Geometric Mean Arithmetic Mean (CV %) | ||||
| Parameter | Test* | Reference † | % Ratio of Geometric Means | 90% Confidence Interval |
AUC0→t (hr.ng/mL) | 1434.0 1475.1 (25.3) | 1389.0 1428.1 (25.0) | 103.2 | 98.3-108.4 |
AUC0→∞ (hr.ng/mL) | 1483.0 1523.6 (25.0) | 1435.0 1474.0 (24.6) | 103.3 | 98.6-108.4 |
| Cmax (ng/mL) | 198.3 203.7 (25.2) | 195.1 200.7 (26.3) | 101.6 | 95.6-108.0 |
| Tmax§ (h) | 2.0 (0.7-4.5) | 1.7 (0.7-4.5) | ||
| T½$ (h) | 9.7 (13.0) | 9.7 (13.0) | ||
* Auro-Candesartan HCT (Candesartan Cilexetil and Hydrochlorothiazide) Tablets, 32 mg/25 mg by Auro
Pharma Inc.
† ATACAND® PLUS (Candesartan Cilexetil and Hydrochlorothiazide) Tablets, 32 mg/25 mg manufactured by AstraZeneca Canada Inc., Canada were purchased in Canada.
§ Expressed as Median (Range) only.
$ Expressed as arithmetic mean (CV%) only.
15 MICROBIOLOGY
No microbiological information is required for this drug product.
16 NON-CLINICAL TOXICOLOGY
General Toxicology
Acute Toxicity:
Table 5 Acute Toxicity
| Route | Species | Sex | LD50 (mg/kg) values |
|---|---|---|---|
| oral gavage | rat | Male Female | >2000 candesartan cilexetil & >1000 HCTZ |
Chronic Toxicity: The toxic potential of candesartan cilexetil was evaluated in a series of repeated-dose oral toxicity studies of ≤ 13 weeks in rats and dogs. The no toxic effect dose level for candesartan cilexetil/hydrochlorothiazide was 1/10 mg/kg/day in rats.
Table 6 Toxicity Upon Repeated Oral Administration
| Species/ Strain | No. Of Animals per Group | Duration and Route of Adminis- tration | Daily Dose candesartan cilexetil/HCTZ (mg/kg) | Results |
|---|---|---|---|---|
Rat / Fischer 344/DuCrj | 10M + 10F | 4 weeks dietary | 0/0 0/10 300/0 3/10 30/10 300/10 | No deaths, and no treatment related abnormalities in clinical signs, urine chemistry, or gross pathology, or upon urine analysis or ophthalmic examinations. Decr.in body weight, food consumption, heart weight and osmolality and increase in incidence of basophilic renal tubules, hypertrophy of juxtaglomerular cells for grps 300/0 and 300/10. Grps 300/0, 30/10 and 300/10 had an incr. in urine output, water intake, urea nitrogen, total chol. and atrophy of zona glomerulosa and a decr.in osmolality, erythrocytes, hematocrit and hemoglobin conc. and triglycerides. Grps 30/10 and 300/10 had an incr. in creatinine, ALP, LAP and inorganic phosphorus. M in grps 300/0 and 30/10 had an incr. in potassium as well as M and F in grp 300/10. F in grp 3/10 had an incr. in urine output, water intake, ALP, LAP and atrophy of the zona glomerulosa. F in grp 0/10 and 3/10 had a decr.in chloride. |
Rat / Fischer 344/DuCrj | 10M + 10F | 13 weeks dietary | 0/0 1/10 10/10 100/10 | No deaths, and no abnormal signs. No toxicokinetic interactions occurred btw candesartan cilexetil and HCTZ. Grps 10/10 and 100/10 had an increase in basophilia of the renal tubules, calcification in the renal papilla, blood urea nitrogen, inorganic phosphorus and a decr.in calcium, total protein, red blood cells, hemoglobin and hematocrit. The 100/10 grp had atrophy of the zona glomerulosa, urinary casts, white kidney patches, and an incr. in creatinine, and corpuscular volume. |
| Species/ Strain | No. Of Animals per Group | Duration and Route of Adminis- tration | Daily Dose candesartan cilexetil/HCTZ (mg/kg) | Results |
|---|---|---|---|---|
Rat / Fischer 344/DuCrj | 10M + 10F | 13 weeks dietary | 0/0 0/30 100/0 100/30 | No deaths occurred and no abnormal signs. Toxic effects were seen in the 100/30 grp which included basophilic renal tubules and erosion/regeneration of the stomach. Decr.in body weight, urine osmolality and increases in water intake, urine volume, serum blood nitrogen and pathological changes noted above increased with concurrent administration. The 100/30 grp had an incr. in serum creatinine and inorganic phosphorus as well as shortening of prothrombin time and activated partial thromboplastin time. |
| Beagle | 3M + 3F | 4 weeks dietary | 0/0 0/10 4/0 20/0 100/0 4/10 20/10 100/10 | 2 M were sacrificed after the 11th and 24th dose and 3 F died: 2 after the 10th dose and 1 after the 14th dose in the 100/10 (N=6) grp due to decreased locomotor activity, lack of food consumption and increase in plasma urea nitrogen concentration and creatinine. Increases in regeneration of renal tubules, hypertrophy of the juxtaglomerular cells, erosion or ulcer of the stomach were noted in most of the 100/10 grp and in some animals of the 20/10 group. Other abnormalities were decreases in osmolality, reticulocytes, chloride and potassium and increases in urea nitrogen, calcium, inorganic potassium, creatinine, erthyrocytes, hematocrit and hemoglobin which were observed in various groups other than the control. |
| Species/ Strain | No. Of Animals per Group | Duration and Route of Adminis- tration | Daily Dose candesartan cilexetil/HCTZ (mg/kg) | Results |
|---|---|---|---|---|
| Beagle | 3M + 3F | 13 weeks dietary | 0/0 0.8/10 4/10 20/10 | 2 F were sacrificed after the 31st dose and 38th dose in the 20/10 grp due to a decr.in movement and food consumption, hypothermia, paleness of conjuctival and oral mucosa and constipation. These F had an incr. in serum urea nitrogen, creatinine, inorganic phosphates and a decr.in sodium and chloride. The kidneys had tubular dilatation, severe regeneration of renal tubules, hypertrophy of juxtaglomerular cells and vacuolization and calcification in papilla. The stomach had erosion, mucosal hemorrhage and calcification and glands demonstrated atrophy. Decr.in urinary osmotic pressure for grp 20/10 and F of grps 0.8/10 and 4/10 as well as an incr. in sodium content for the latter. All other animals sacrificed on schedule showed no treatment change except for histological changes to kidneys. |
| Beagle | 3M + 3F | 13 weeks dietary | 0/0 4/0 0/30 4/30 | Treatment related deaths or severe toxic signs or symptoms did not occur in any animal. Hypertrophy of the juxtaglomerular cells occurred in the 4/0 and 4/30 animals. Increased urine vol. and decr. serum potassium occurred in the 0/30 and 4/30 grps. |
Carcinogenicity
No carcinogenicity studies were carried out with the candesartan cilexetil/hydrochlorothiazide combination.
Candesartan cilexetil: The carcinogenic potential of candesartan cilexetil was studied in rats after administration in the diet for 24 months. Dose levels were 100, 300 and 1000 mg/kg/day (50 male and 50 female rats per group). No alteration in tumour profile was observed. A 2-year oral gavage study of candesartan cilexetil in mice was performed at daily dosages of 3, 10, 30 and 100 mg/kg/day. There was no alteration in the tumour profile.
There is no evidence that candesartan cilexetil is carcinogenic.
Hydrochlorothiazide: According to the experimental data available, hydrochlorothiazide revealed inconsistent evidence of carcinogenic activity in rats and mice, with conflicting evidence of hepatic adenoma in male mice at the highest dose and adrenal pheocytochroma in one rat study but not in another. Current evidence is inadequate to draw a clear conclusion for a carcinogenic effect of hydrochlorothiazide in animals.
The mutagenic potential was assessed in a series of in vitro and in vivo test systems. While some positive results were obtained in vitro, all in vivo studies provided negative results. Hydrochlorothiazide enhanced the UVA-induced formation of pyrimidine dimers in vitro and in the skin of repair deficient mice following oral treatment. It is therefore concluded that although there is no relevant mutagenic potential in vivo, hydrochlorothiazide could enhance the genotoxic effects of UVA light. This mechanism of photosensitization could be associated with a higher risk for non-melanoma skin cancer.
Genotoxicity
The studies performed show that the 1:2 mixture of candesartan cilexetil and hydrochlorothiazide is devoid of genotoxic activity in a range of in vitro studies in bacteria and in in vivo studies. These studies showed that candesartan cilexetil did not have a synergistic mutagenic effect when administered with hydrochlorothiazide. Taking into consideration all the studies conducted on the components and the combination it is concluded that the probability that the combination of candesartan cilexetil and hydrochlorothiazide being genotoxic to humans is extremely low.
Reproductive and Developmental Toxicology
Reproductive studies were performed in rats, mice and rabbits. In rats, effects upon the maternal as well as upon the fetal body weight were recorded at 100/10 mg/kg/day and a minor skeletal effect was recorded upon the fetuses at 30/10 mg/kg/day with candesartan cilexetil/hydrochlorothiazide. The no observed adverse effect dose level in rats was 10/10 mg/kg of candesartan cilexetil and hydrochlorothiazide combination. The maternal toxicity was similar after monotherapy and the combination treatment. In mice, no maternal or fetal effects were seen at doses of up to 1000/10 mg/kg/day. In rabbits maternal toxicity with abortions and deaths was seen with doses from 1/10 mg/kg. The addition of hydrochlorothiazide did not significantly affect the outcome of the fetal development studies in any of the three species tested.
Effects on the development of the kidneys: Animal studies with candesartan cilexetil have demonstrated late fetal and neonatal injury in the kidney. The mechanism is believed to be pharmacologically mediated through effects on the RAAS. The RAAS plays a critical role in kidney development. RAAS blockade has been shown to lead to abnormal kidney development in very young mice. Administering drugs that act directly on the RAAS, such as candesartan cilexetil, can alter normal renal development. Therefore, Auro-Candesartan HCT is contraindicated in children <1 year old (see 2 CONTRAINDICATIONS).
17 SUPPORTING PRODUCT MONOGRAPH
- 1. PrATACAND® PLUS, (Tablets, 16 mg / 12.5 mg, 32 mg / 12.5 mg and 32 mg / 25 mg), Submission Control 268325, Product Monograph, AstraZeneca Canada Inc., Date of Revision: MAR 2, 2023.