


Product Monograph - Belsomra (Merck Canada, 10 mg, 15 mg, 20 mg)
RECENT MAJOR LABEL CHANGES
WARNINGS AND PRECAUTIONS 02/2021
PART I: HEALTH PROFESSIONAL INFORMATION ............................................................... 3
1 INDICATIONS ............................................................................................................... 3
1.1 Pediatrics ............................................................................................................. 3
1.2 Geriatrics ............................................................................................................. 3
2 CONTRAINDICATIONS ................................................................................................ 3
3 DOSAGE AND ADMINISTRATION............................................................................... 3
3.1 Dosing Considerations ......................................................................................... 3
3.2 Recommended Dose and Dosage Adjustment ..................................................... 4
3.3 Missed Dose ........................................................................................................ 5
4 OVERDOSAGE ............................................................................................................. 5
5 DOSAGE FORMS, STRENGTHS, COMPOSITION AND PACKAGING ....................... 5
6 WARNINGS AND PRECAUTIONS ............................................................................... 6
6.1 Special Populations ............................................................................................. 9
6.1.1 Pregnant Women ............................................................................................. 9
6.1.2 Breast-feeding ................................................................................................ 10
6.1.3 Pediatrics ....................................................................................................... 10
6.1.4 Geriatrics ........................................................................................................ 10
6.1.5 Patient Counselling Information ...................................................................... 10
7 ADVERSE REACTIONS ............................................................................................. 11
7.1 Adverse Reaction Overview ............................................................................... 11
7.2 Clinical Trial Adverse Reactions......................................................................... 12
7.3 Less Common Clinical Trial Adverse Reactions ................................................. 13
7.4 Post-Market Adverse Reactions ......................................................................... 14
8 DRUG INTERACTIONS .............................................................................................. 15
8.1 Overview ............................................................................................................ 15
8.2 Drug-Drug Interactions ....................................................................................... 16
8.3 Drug-Food Interactions ...................................................................................... 17
9 ACTION AND CLINICAL PHARMACOLOGY ............................................................. 18
9.1 Mechanism of Action .......................................................................................... 18
9.2 Pharmacodynamics ........................................................................................... 18
9.3 Pharmacokinetics .............................................................................................. 19
10 STORAGE, STABILITY AND DISPOSAL ................................................................... 21
PART II: SCIENTIFIC INFORMATION ................................................................................... 22
11 PHARMACEUTICAL INFORMATION ......................................................................... 22
12 CLINICAL TRIALS ...................................................................................................... 23
12.1 Trial Design and Study Demographics ........................................................... 23
12.2 Study Results ................................................................................................. 24
13 NON-CLINICAL TOXICOLOGY .................................................................................. 28
PATIENT MEDICATION INFORMATION ............................................................................... 31
PART I: HEALTH PROFESSIONAL INFORMATION
1 INDICATIONS
Sleep disturbance may be the presenting manifestation of a physical and/or psychiatric disorder. Consequently, a decision to initiate symptomatic treatment of insomnia should only be made after the patient has been carefully evaluated.
BELSOMRA® (suvorexant) is indicated for the treatment of insomnia, characterized by difficulties with sleep onset and/or sleep maintenance.
The clinical trials performed in support of efficacy were up to 3 months duration in adults and elderly patients.
1.1 Pediatrics
Pediatrics (< 18 years of age): The safety and effectiveness of BELSOMRA® in pediatric patients have not been established. Therefore, treatment with BELSOMRA® is not recommended in this population.
1.2 Geriatrics
Geriatrics (≥ 65 years of age): No clinically meaningful differences in safety or effectiveness were observed between patients ≥ 65 years of age and younger patients at the recommended doses (See WARNINGS AND PRECAUTIONS, Special Populations).
2 CONTRAINDICATIONS
BELSOMRA® is contraindicated in:
- Patients who are hypersensitive to suvorexant or to any ingredient in the formulation, including any non-medicinal ingredient, or component of the container. For a complete listing, see Dosage Forms, Strengths, Composition and Packaging.
- Patients with narcolepsy.
3 DOSAGE AND ADMINISTRATION
3.1 Dosing Considerations
Time to effect of BELSOMRA® may be delayed if taken with or soon after a meal.
3.2 Recommended Dose and Dosage Adjustment
Use the lowest dose effective for the patient.
The recommended initial dose for BELSOMRA® is 10 mg, taken no more than once per night and within 30 minutes of going to bed, with at least 7 hours remaining before the planned time of awakening. If the 10 mg dose is well-tolerated but not effective, the dose can be increased. The maximum recommended dose of BELSOMRA® is 20 mg once daily.
This dose should not be exceeded. Doses higher than 20 mg were evaluated in clinical trials but were associated with significantly more adverse effects and an unfavourable risk-benefit balance (see CLINICAL TRIALS).
Pediatrics (<18 years of age): The safety and efficacy of BELSOMRA® have not been evaluated in patients less than 18 years of age. Therefore, treatment with BELSOMRA® is not recommended in this population.
Geriatrics (≥ 65 years of age): Dosage adjustments in geriatrics are not generally necessary (See ACTION AND CLINICAL PHARMACOLOGY, Pharmacokinetics, Special Populations and Conditions, Geriatrics)
Patients with Hepatic Impairment: No dose adjustment is required in patients with mild and moderate hepatic impairment. BELSOMRA® has not been studied in patients with severe hepatic impairment and is not recommended for these patients (See ACTION AND CLINICAL PHARMACOLOGY, Pharmacokinetics, Special Populations and Conditions, Hepatic Insufficiency).
Patients with Renal Impairment: No dose adjustment is required in patients with renal impairment (See ACTION AND CLINICAL PHARMACOLOGY, Pharmacokinetics, Special Populations and Conditions, Renal Insufficiency).
Other Special Populations
Exposure to BELSOMRA® is increased in obese compared to non-obese patients, and in women compared to men. Particularly in obese women, the increased risk of exposure-related adverse effects should be considered before increasing the dose (See ACTION AND CLINICAL PHARMACOLOGY, Pharmacokinetics, Special Populations and Conditions, Population Pharmacokinetic Analysis).
Use with CNS Depressants
When BELSOMRA® is combined with other CNS depressant drugs, dosage adjustment of BELSOMRA® and/or the other drug(s) may be necessary because of potentially additive effects (See WARNINGS AND PRECAUTIONS, General, CNS Depressant Effects and Daytime Impairment, including Driving Impairment).
Use with CYP3A Inhibitors
BELSOMRA® is not recommended for use with strong or moderate CYP3A inhibitors as the exposure to suvorexant is increased (See WARNINGS AND PRECAUTIONS, General, Drug Interactions- Inhibitors of CYP3A; DRUG INTERACTIONS, Effects of Other Drugs on BELSOMRA®, CYP3A Inhibitors).
3.3 Missed Dose
If a patient misses a dose, the patient should be instructed not to take BELSOMRA® unless they have the opportunity to get at least 7 hours of sleep before they must be active again. They may continue with their usual dose the following night at bedtime.
4 OVERDOSAGE
There is limited premarketing clinical experience with an overdosage of BELSOMRA®. In clinical pharmacology studies, healthy subjects who were administered morning doses of up to 240 mg of suvorexant showed dose-dependent increases in the frequency and duration of somnolence.
General symptomatic and supportive measures should be used, along with immediate gastric lavage where appropriate. Intravenous fluids should be administered as needed. As in all cases of drug overdose, vital signs should be monitored and general supportive measures employed. The value of dialysis in the treatment of overdosage has not been determined. As suvorexant is highly protein-bound, hemodialysis is not expected to contribute to elimination of suvorexant.
As with the management of all overdosage, the possibility of multiple drug ingestion should be considered. Consider contacting a poison control center for up-to-date information on the management of hypnotic drug product overdosage.
| For management of a suspected drug overdose, contact your regional poison control centre. |
5 DOSAGE FORMS, STRENGTHS, COMPOSITION AND PACKAGING
Table – Dosage Forms, Strengths, Composition and Packaging.
| *contains hypromellose, lactose monohydrate, titanium dioxide, and triacetin. The film coating for the 10 mg tablets also contains FD&C Blue #1/Brilliant Blue FCF Aluminum Lake and iron oxide yellow. |
- BELSOMRA® 10 mg tablets are green, round, film-coated tablets with “33” on one side and plain on the other side.
| Route of Administration | Dosage Form / Strength/Composition | Non-medicinal Ingredients |
| Oral | tablet 10 mg suvorexant 15 mg suvorexant 20 mg suvorexant |
|
- BELSOMRA® 15 mg tablets are white, oval, film coated tablets, with Merck logo on one side and “325’’ on the other.
- BELSOMRA® 20 mg tablets are white, round, film coated tablets, with Merck logo and “335’’on one side and plain on the other.
BELSOMRA® tablets are packaged in blisters of 10 with 30 tablets per carton.
6 WARNINGS AND PRECAUTIONS
General
CNS Depressant Effects and Daytime Impairment, including Driving Impairment
BELSOMRA® is a central nervous system (CNS) depressant that can impair daytime wakefulness even when used as prescribed. Prescribers should monitor for somnolence and CNS depressant effects, but impairment can occur in the absence of symptoms, and may not be reliably detected by ordinary clinical exam (i.e., less than formal testing of daytime wakefulness and/or psychomotor performance). CNS depressant effects may persist in some patients for up to several days after discontinuing BELSOMRA®.
BELSOMRA® can impair driving skills and may increase the risk of falling asleep while driving. Discontinue or decrease the dose in patients who drive if daytime somnolence develops. In a study of healthy adults, driving ability was impaired in some individuals taking 20 mg BELSOMRA® (See ACTION AND CLINICAL PHARMACOLOGY, Pharmacodynamics, Effects on Driving). Although pharmacodynamic tolerance or adaptation to some adverse depressant effects of BELSOMRA® may develop with daily use, patients using BELSOMRA® should be cautioned against next-day driving and other activities requiring full mental alertness until they experience how the drug affects them the next day. Patients should be informed that impairment can be present despite feeling fully awake. The risks are greater for patients using the 20 mg dose; however, patients taking lower doses of BELSOMRA® should also be cautioned because there is individual variation in sensitivity to BELSOMRA®.
The lowest effective dose for the patient should be used.
Patients should be advised not to consume alcohol or other sedative hypnotics in combination with BELSOMRA® because of additive effects (See DRUG INTERACTIONS, CNS-active Agents). If concomitant use of another CNS depressant or a drug that increases BELSOMRA® blood levels is clinically warranted, dosage adjustments may be necessary.
The risk of next-day impairment, including impaired driving, is increased if BELSOMRA® is taken with less than a full night of sleep remaining, if a higher than the recommended dose is taken, if co-administered with other CNS depressants, or if co-administered with other drugs that increase blood levels of BELSOMRA®. Patients should be cautioned against driving and other activities requiring complete mental alertness if BELSOMRA® is taken in these circumstances.
Because BELSOMRA® can cause drowsiness, patients, particularly the elderly, are at higher risk of falls.
Need to Evaluate for Co-morbid Diagnoses
Because sleep disturbances may be the presenting manifestation of a physical and/or psychiatric disorder, treatment of insomnia should be initiated only after careful evaluation of the patient. The failure of insomnia to remit after 7 to 10 days of treatment may indicate the presence of a primary psychiatric and/or medical illness that should be evaluated. Worsening of insomnia or the emergence of new cognitive or behavioral abnormalities may be the result of an unrecognized underlying psychiatric or physical disorder and can emerge during the course of treatment with hypnotic drugs such as BELSOMRA®.
Abnormal Thinking, Behavioural Changes and Complex Sleep-related Behaviours
A variety of cognitive and behavioural changes (e.g., amnesia, anxiety, hallucinations and other neuro-psychiatric symptoms) have been reported to occur in association with the use of hypnotics such as BELSOMRA®.
Complex sleep-related behaviours such as "sleep-driving" (i.e., driving while not fully awake after taking a hypnotic) and other complex behaviours (e.g., preparing and eating food, making phone calls, leaving the house or having sex), with amnesia for the event, have been reported in association with the use of hypnotics such as BELSOMRA®. These events can occur in hypnotic-naïve as well as in hypnotic-experienced persons. Although complex sleep-related behaviours may occur with BELSOMRA® alone at therapeutic doses, the use of alcohol and other CNS depressants may increase the risk of such behaviours.
While complex sleep-related behaviours have been reported in patients with or without history of sleepwalking, it is possible that some predisposed patients are at increased risk of experiencing these complex behaviours during treatment with BELSOMRA®. Patients with other disorders known to affect sleep and induce frequent awakenings (e.g. sleep apnea, Periodic Limb Movement Disorder, Restless Legs Syndrome) may be also at increased risk of complex sleep-related behaviours.
Due to the risk to the patient and the community, discontinuation of BELSOMRA® should be strongly considered for patients who report any complex sleep behaviour.
Worsening of Depression/Suicidal Ideation
In clinical studies, a dose-dependent increase in suicidal ideation was observed in patients taking BELSOMRA® as assessed by questionnaire. Immediately evaluate patients with suicidal ideation or any new behavioral sign or symptom.
In primarily depressed patients treated with sedative-hypnotics, worsening of depression, and suicidal thoughts and actions (including completed suicides) have been reported. Suicidal tendencies may be present in such patients and protective measures may be required. Intentional overdose is more common in this group of patients; therefore, the lowest number of tablets that is feasible should be prescribed for the patient at any one time.
Patients, their families, and their caregivers should be encouraged to be alert to worsening of depression, including suicidal thoughts and actions. Such symptoms should be reported to the patient's prescriber or health professional. The emergence of any new behavioral sign or symptom of concern requires careful and immediate evaluation.
Patients with Compromised Respiratory Function
Effect of BELSOMRA® on respiratory function should be considered if prescribed to patients with compromised respiratory function. BELSOMRA® has not been studied in patients with severe obstructive sleep apnea (OSA) or severe chronic obstructive pulmonary disease (COPD) (See WARNINGS AND PRECAUTIONS, Respiratory).
Sleep Paralysis, Hypnagogic/Hypnopompic Hallucinations, Cataplexy-like Symptoms
Sleep paralysis, an inability to move or speak for up to several minutes during sleep-wake transitions, and hypnagogic/hypnopompic hallucinations, including vivid and disturbing perceptions by the patient, can occur with the use of BELSOMRA®. Prescribers should explain the nature of these events to patients when prescribing BELSOMRA®.
Symptoms similar to mild cataplexy can occur, with risk increasing with the dose of BELSOMRA. Such symptoms can include periods of muscular weakness, commonly in the legs, lasting from seconds to a few minutes, can occur both at night and during the day, and may not be associated with an identified triggering event (e.g., laughter or surprise).
Drug Interactions - Inhibitors of CYP3A
Concomitant use of BELSOMRA® with strong or moderate CYP3A inhibitors is not recommended (see DRUG INTERACTIONS, Drug-Drug Interactions, Effects of Other Drugs on BELSOMRA®, CYP3A Inhibitors).
Lactose
Lactose is a non-medicinal ingredient in BELSOMRA®. Patients with rare hereditary diseases of galactose intolerance (galactosemia or glucose-galactose malabsorption) should not take BELSOMRA®.
Dependence/Tolerance and Abuse Liability
As with other hypnotics, care should be taken when prescribing BELSOMRA® to individuals with a history of addiction to, or abuse of, drugs or alcohol due to risk of misuse or abuse.
Abuse: In an abuse liability study conducted in recreational polydrug users (n=36), suvorexant (40, 80 and 150 mg) produced similar effects as zolpidem (15, 30 mg) on subjective ratings of "drug liking" and other measures of subjective drug effects.
Dependence/Withdrawal: In completed clinical studies with BELSOMRA®, there was no evidence for physical dependence with the prolonged use of BELSOMRA®.
In 3-month controlled safety and efficacy studies (Studies 1 and 2), withdrawal effects were assessed following discontinuation in non-elderly adult patients who received BELSOMRA® 40 mg or 20 mg and elderly patients who received BELSOMRA® 30 mg or 15 mg. The analysis showed no clear evidence of withdrawal in the overall study population based on assessment of patient responses to the Tyrer Withdrawal Symptom Questionnaire on 3 consecutive nights after discontinuation, or assessment of pre-specified-hypnotic withdrawal-related adverse events during a 1-week period following the discontinuation of BELSOMRA®.
Rebound Effects: In 3-month controlled safety and efficacy trials (Studies 1 and 2), rebound insomnia was assessed following discontinuation of BELSOMRA® relative to placebo and baseline in non-elderly adult patients receiving BELSOMRA® 40 mg or 20 mg and in elderly patients receiving BELSOMRA® 30 mg or 15 mg. Based on the overall assessment of both doses of BELSOMRA® evaluated in non-elderly and elderly patients, no effects were seen on measures of sleep onset. Effects were seen on some sleep maintenance measures following BELSOMRA® discontinuation but had the characteristics of the return of insomnia symptoms and did not appear to be consistent with clinically meaningful rebound insomnia.
Driving and Operating Machinery
See WARNINGS AND PRECAUTIONS, General, CNS Depressant Effects and Daytime Impairment, including Driving Impairment.
Hepatic/Biliary/Pancreatic
Patients with Severe Hepatic Impairment
BELSOMRA® has not been studied in patients with severe hepatic impairment and is not recommended for these patients (See ACTION AND CLINICAL PHARMACOLOGY, Pharmacokinetics, Special Populations and Conditions, Hepatic Insufficiency).
Respiratory
Effects of BELSOMRA® on respiratory function should be considered if prescribed to patients with compromised respiratory function.
Obstructive Sleep Apnea
The respiratory depressant effect of BELSOMRA® was evaluated after one night and after four consecutive nights of treatment in a randomized, placebo-controlled, 2-period crossover study in patients (n=26) with mild to moderate obstructive sleep apnea. Following once-daily doses of 40 mg, the mean Apnea/Hypopnea Index treatment difference (suvorexant – placebo) on Day 4 was 2.7 (90% CI: 0.22 to 5.09), but there was wide inter- and intra-individual variability such that clinically meaningful respiratory effects of BELSOMRA® in obstructive sleep apnea cannot be excluded. BELSOMRA® has not been studied in patients with severe obstructive sleep apnea (See WARNINGS AND PRECAUTIONS, Patients with Compromised Respiratory Function).
Chronic Obstructive Pulmonary Disease
The respiratory depressant effect of BELSOMRA® was evaluated after one night and after four consecutive nights of treatment in a randomized, placebo-controlled, 2-period crossover study in patients (n=25) with mild to moderate chronic obstructive pulmonary disease (COPD). BELSOMRA® (40 mg in non-elderly, 30 mg in elderly) had no respiratory depressant effects in patients with mild to moderate COPD, as measured by oxygen saturation. There was wide inter- and intra-individual variability such that clinically meaningful respiratory effects of BELSOMRA® in COPD cannot be excluded. BELSOMRA® has not been studied in patients with severe COPD (See WARNINGS AND PRECAUTIONS, Patients with Compromised Respiratory Function).
6.1 Special Populations
6.1.1 Pregnant Women
No clinical studies have been conducted in pregnant women. BELSOMRA® should be used during pregnancy only if the potential benefit justifies the potential risk to the fetus.
Teratogenicity was not observed in pregnant rats or rabbits treated during the period of organogenesis. In rats, developmental toxicity was limited to a decrease in fetal body weights. In rabbits, there was no evidence of developmental toxicity. The maternal exposure in rats and rabbits at the no-effect dose was 25-times and 39-times the clinical exposure at the MRHD (20 mg), respectively.
Following oral administration to rats throughout gestation and lactation, effects in the offspring were limited to a transient decrease in body weight at the highest dose tested. The maternal exposure at the no-effect dose was 25-times the clinical exposure at the MRHD (20 mg).
6.1.2 Breast-feeding
Suvorexant and a hydroxy-suvorexant metabolite were excreted in rat milk at levels higher (9 and 1.5 times, respectively) than that in maternal plasma. It is not known whether this drug is secreted in human milk. Because many drugs are excreted in human milk, precaution should be exercised.
6.1.3 Pediatrics
Pediatrics (< 18 years of age): Safety and effectiveness of BELSOMRA® in pediatric patients have not been established. Therefore, treatment with BELSOMRA® is not recommended.
6.1.4 Geriatrics
Geriatrics (≥ 65 years of age): Of the total number of patients treated with BELSOMRA® (n=1784) in controlled clinical safety and efficacy studies, 829 patients were 65 years and over, and 159 patients were 75 years and over. No clinically meaningful differences in safety or effectiveness were observed between these patients and younger patients at the recommended doses (See INDICATIONS; CLINICAL TRIALS, Study results; ACTION AND CLINICAL PHARMACOLOGY, Pharmacokinetics, Special Populations and Conditions, Population Pharmacokinetic Analysis).
Because BELSOMRA can increase drowsiness, patients, particularly the elderly, are at a higher risk of falls (See WARNINGS AND PRECAUTIONS).
6.1.5 Patient Counselling Information
The physician should advise the patient (and/or their caregiver, if relevant) about the benefits and risks associated with treatment with sedative-hypnotics and should counsel them on its appropriate use. The physician should instruct them to read carefully the Patient Medication Information Leaflet before starting treatment with BELSOMRA. Review the BELSOMRA® Patient Medication Information Leaflet with every patient prior to initiation of treatment.
Patients receiving BELSOMRA® should be given the following instructions by the physician:
CNS Depressant Effects and Next-Day Impairment: Tell patients that BELSOMRA® has the potential to cause next-day impairment, and that this risk is increased with higher doses or if dosing instructions are not carefully followed. Patients should be cautioned against next-day driving and other activities requiring full mental alertness until they know how the drug affects them the next day. Tell patients to contact their healthcare provider if daytime somnolence develops. Inform patients that impairment can occur
- despite feeling fully awake. Advise patients that increased drowsiness may increase the risk of falls in some patients.
- Sleep-Driving and Other Complex Sleep-related Behaviours: Instruct patients to inform their families that hypnotics, like BELSOMRA®, have been associated with getting out of bed and doing activities while not being fully awake, without memory of these activities the next morning. These complex sleep-related behaviours include driving a car (“sleep-driving”), preparing and eating food, making phone calls, leaving the house, having sex, etc. Tell patients and their families to call their healthcare provider if they find out that the patient has done such activities.
Sleep Paralysis, Hypnagogic/Hypnopompic Hallucinations, Cataplexy-like Symptoms: Inform patients that sleep paralysis and hypnagogic/hypnopompic hallucinations, including vivid and disturbing perceptions by the patient, can occur with the use of BELSOMRA®. Prescribers should explain the nature of these events to patients when prescribing BELSOMRA®.
Inform patients that muscular weakness similar to mild cataplexy, commonly in the legs lasting from seconds to a few minutes, can occur both at night and during the day, and may not be associated with an identified triggering event (e.g., laughter or surprise). Tell the patient to contact their healthcare provider if any of these events occur.
- Suicide: Tell patients, and/or caregivers to report any worsening of depression or suicidal thoughts immediately.
7 ADVERSE REACTIONS
7.1 Adverse Reaction Overview
Most Common Adverse Reactions: In clinical trials of patients with insomnia treated with BELSOMRA® 15 mg or 20 mg, the most common adverse reaction (reported in 5% or more of patients treated with BELSOMRA® and at least twice the placebo rate) was somnolence (BELSOMRA®7%; placebo 3.0%).
Dose Relationship for Adverse Reactions: There is evidence of a dose relationship for many of the adverse reactions associated with BELSOMRA® use, particularly for certain CNS adverse reactions. In a Phase 2 placebo-controlled crossover study (Study 3) in non-elderly adult patients treated for up to one month with BELSOMRA® at doses of 10 mg, 20 mg, 40 mg (2 times the maximum recommended dose) or 80 mg (4 times the maximum recommended dose), BELSOMRA® was associated with a dose-related increase in somnolence.
Adverse Reactions Resulting in Discontinuation of Treatment: The incidence of discontinuation due to adverse reactions for patients treated with 15 mg or 20 mg of BELSOMRA® was 3% compared to 5% for placebo. No individual adverse reaction led to discontinuation at an incidence ≥1%.
The only adverse reaction resulting in discontinuation in at least 1% in subjects treated with higher than recommended doses of BELSOMRA® was somnolence (1%).
7.2 Clinical Trial Adverse Reactions
Because clinical trials are conducted under very specific conditions, the adverse reaction rates observed in the clinical trials may not reflect the rates observed in practice and should not be compared to the rates in the clinical trials of another drug. Adverse reaction information from clinical trials is useful for identifying drug-related adverse events and for approximating rates.
In 3-month placebo-controlled efficacy trials (Study 1 and Study 2), 1263 patients were exposed to BELSOMRA® including 493 patients who received BELSOMRA® 15 mg or 20 mg (see Table 1).
In a long-term safety study, additional patients (n=521) were treated with BELSOMRA® at higher than recommended doses, including a total of 160 patients who received BELSOMRA® for at least one year.
Table 1: Exposure to BELSOMRA® 15 mg or 20 mg in Study 1 and Study 2
| Patients Treated | BELSOMRA® 15 mg | BELSOMRA® 20 mg |
| For ≥ 1 Day (n) | 202 | 291 |
| Men (n) | 69 | 105 |
| Women (n) | 133 | 186 |
| Mean Age (years) | 70 | 45 |
| For ≥ 3 Months (n) | 118 | 172 |
The pooled safety data described below (see Table 2) reflect the adverse reaction profile during the first 3 months of treatment.
Adverse Reactions Observed in Placebo-Controlled Clinical Studies
Table 2 shows the percentage of patients with adverse reactions during the first three months of treatment, based on the pooled data from 3-month controlled efficacy trials (Study 1 and Study 2).
At doses of 15 or 20 mg, the incidence of somnolence was higher in females (8%) than in males (3%). Of the adverse reactions reported in Table 2, the following occurred in women at an incidence of at least twice that in men: headache, abnormal dreams, dry mouth, cough, and upper respiratory tract infection.
The adverse reaction profile in elderly patients was generally consistent with non-elderly patients. The adverse reactions reported during long-term treatment up to 1 year were generally consistent with those observed during the first 3 months of treatment.
Table 2: Percentage of Patients with Adverse Reactions Incidence ≥2% and Greater than Placebo in 3-Month Controlled Efficacy Trials (Study 1 and Study 2)
Placebo N=767 | BELSOMRA® (20 mg in non-elderly or 15 mg in elderly patients) N=493 | |
| % | % | |
| Gastrointestinal Disorders | ||
| Diarrhea | 1 | 2 |
| Dry mouth | 1 | 2 |
| Infections and Infestations | ||
| Upper respiratory tract infection | 1 | 2 |
| Nervous System Disorders | ||
| Headache | 6 | 7 |
| Somnolence | 3 | 7 |
| Dizziness | 2 | 3 |
| Psychiatric Disorders | ||
| Abnormal dreams | 1 | 2 |
| Respiratory, Thoracic and Mediastinal Disorders | ||
| Cough | 1 | 2 |
| Injury, Poisoning and Procedural Complications | ||
| Drug administration error | 2 | 3 |
7.3 Less Common Clinical Trial Adverse Reactions
The following additional selected adverse events were reported in patients treated with BELSOMRA®15 mg or 20 mg at an incidence of <2% and greater than placebo during the first three months of treatment based on the pooled data from the two placebo-controlled clinical studies. The adverse events are further classified within body system categories as follows: frequent adverse events are defined as those occurring in at least 1% of patients and infrequent adverse events are those occurring in fewer than 1% of patients. A causal relationship of these events to BELSOMRA® is uncertain.
Cardiac disorders
Infrequent: Palpitations
Eye disorders
Infrequent: Dry eye
Gastrointestinal disorders
Frequent: Dyspepsia
Infrequent: Constipation, Gastrooesophageal reflux disease
General disorders and administration site conditions
Frequent: Pyrexia
Infrequent: Feeling abnormal, Hangover
Infections and infestations
Frequent: Gastroenteritis
Infrequent: Cystitis
Injury, poisoning and procedural complications
Infrequent: Contusion
Investigations
Frequent: Alanine aminotransferase increased
Infrequent: Aspartate aminotransferase increased
Musculoskeletal and connective tissue disorders
Infrequent: Muscular weakness, Musculoskeletal pain
Nervous system disorders
Infrequent: Disturbance in attention, Dysgeusia, Lethargy, Sleep paralysis
Psychiatric disorders
Frequent: Nightmare
Infrequent: Agitation, Hypnagogic hallucination, Hypnopompic hallucination, Suicidal ideation
Respiratory, thoracic and mediastinal disorders
Infrequent: Dyspnea, Oropharyngeal pain
Skin and subcutaneous tissue disorders
Infrequent: Eczema, Hyperhidrosis, Pruritus
Vascular disorders
Infrequent: Hypertension
7.4 Post-Market Adverse Reactions
The following adverse reactions have been identified during post-approval use of BELSOMRA®. Because these reactions are reported voluntarily from a population of uncertain size, it is not always possible to reliably estimate their frequency or establish a causal relationship to drug exposure.
Cardiac disorders: tachycardia
Gastrointestinal disorders: nausea, vomiting
Nervous system disorders: psychomotor hyperactivity
Psychiatric disorders: anxiety
8 DRUG INTERACTIONS
8.1 Overview
CNS-active Agents
Patients should be advised against combined use of BELSOMRA® with other CNS depressants (e.g. alcohol, other sedative hypnotics, opioids, tricyclic antidepressants, etc.) because of the potential for additive effects on psychomotor performance. If concomitant use of another CNS depressant is warranted, a dosage adjustment of BELSOMRA® and/or the other drug(s) may be necessary (See WARNINGS AND PRECAUTIONS, General, CNS Depressant Effects and Daytime Impairment, including Driving Impairment).
Effects of Other Drugs on BELSOMRA®
Metabolism by CYP3A is the major elimination pathway for suvorexant.
CYP3A Inhibitors
Concomitant use of BELSOMRA® with strong inhibitors of CYP3A (e.g., ketoconazole, itraconazole, posaconazole, clarithromycin, nefazodone, ritonavir, saquinavir, nelfinavir, indinavir, boceprevir, telaprevir, telithromycin and conivaptan) is not recommended (See WARNINGS AND PRECAUTIONS, General, Drug Interactions-Strong Inhibitors of CYP3A).
Concomitant administration of BELSOMRA® with moderate CYP3A inhibitors (e.g., amprenavir, aprepitant, atazanavir, ciprofloxacin, diltiazem, erythromycin, fluconazole, fosamprenavir, grapefruit juice, imatinib, verapamil) is not recommended (See DOSAGE AND ADMINISTRATION, Recommended Dose and Dose Adjustment).
CYP3A Inducers
Suvorexant exposure can be substantially decreased when co-administered with strong CYP3A inducers (e.g., rifampin, carbamazepine and phenytoin). The efficacy of BELSOMRA® may be reduced.
Effects of BELSOMRA® on Other Drugs
Suvorexant is a weak inhibitor of CYP3A and the intestinal P-glycoprotein (P-gp) transporter following consecutive, multiple-dose administration.
Midazolam
Concomitant administration of suvorexant with midazolam (a sensitive CYP3A substrate) slightly increased midazolam exposure. For most drugs metabolized by CYP3A, suvorexant is not expected to increase plasma concentrations to a clinically significant degree.
Digoxin
Concomitant administration of suvorexant with digoxin slightly increased digoxin levels due to inhibition of intestinal P-gp. Digoxin concentrations should be monitored as clinically indicated when co-administering BELSOMRA® with digoxin.
8.2 Drug-Drug Interactions
Effects of other co-administered drugs on BELSOMRA®
The effects of co-administered drugs on the pharmacokinetics of suvorexant have been assessed in drug-drug interaction studies in healthy subjects. Strong (e.g., ketoconazole) and moderate (e.g., diltiazem) CYP3A inhibitors significantly increased suvorexant exposure and prolonged the elimination half-life of suvorexant. A strong CYP3A inducer (e.g., rifampin) substantially decreased suvorexant exposure (see Table 3).
Table 3. Effects of Other Drugs on the Pharmacokinetics of Suvorexant
Geometric Mean Ratio [90% CI] of Suvorexant PK with/without Co-administered Drug | ||||||||||
| Co-administered Drug | Regimen of Co-administered Drug | Suvorexant Regimen | N | AUC | Cmax | Clinical Comment | ||||
Ketoconazole (strong CYP3A inhibitor) | 400 mg QD x 11 days | 4 mg single dose | 10 | 2.79 [2.35, 3.31] | 1.23 [1.05, 1.44] | Not Recommended | ||||
| Diltiazem (moderate CYP3A inhibitor) | 240 mg QD x 6 days | 20 mg single dose | 20 | 2.05 [1.82, 2.30] | 1.22 [1.09, 1.36] | Not Recommended | ||||
Rifampin (strong CYP3A inducer) | 600 mg QD x 17 days | 40 mg single dose | 10 | 0.12 [0.11, 0.14] | 0.36 [0.31, 0.42] | Efficacy may be reduced | ||||
Abbreviations: CI=confidence interval; AUC=area under the plasma concentration-time curve; Cmax=maximum observed concentration; QD=once-daily
Effects of BELSOMRA® on other co-administered drugs
In vitro metabolism studies demonstrate that suvorexant has a potential to inhibit CYP3A and intestinal P-gp; however, suvorexant is unlikely to cause clinically significant inhibition of human CYP1A2, CYP2B6, CYP2C8, CYP2C9, CYP2C19 or CYP2D6. In addition, no clinically meaningful inhibition of OATP1B1, BCRP and OCT2 transporters is anticipated. Chronic administration of suvorexant is unlikely to induce the metabolism of drugs metabolized by major CYP isoforms. The effects of suvorexant on the pharmacokinetics of co-administered drugs have been assessed in drug-drug interaction studies (see Table 4).
Table 4. Effects of Suvorexant on the Pharmacokinetics of Other Drugs
Geometric Mean Ratio [90% CI] of Co-administered Drug PK with/without Suvorexant | ||||||||||||
| Co-administered Drug | Regimen of Co-administered Drug | Suvorexant Regimen | N | AUC | Cmax | Clinical Comment | ||||||
| Midazolam (CYP3A substrate) | 2 mg single dose | 80 mg QD x 14 days | 12 | 1.47 [1.30, 1.67] | 1.23 [1.07, 1.41] | No dose adjustment | ||||||
| Combined Oral Contraception (EE and Norgestimate) | EE 0.035 mg Norgestimate 0.250 mg | 40 mg QD x 18 days | 20 | EE: 1.07 [0.99, 1.16] NGMN: 1.16 [1.11, 1.20] | EE: 0.94 [0.83, 1.06] NGMN: 1.08 [0.95, 1.23] | No dose adjustment | ||||||
| Warfarin (CYP2C9 substrate) | 30 mg single dose | 40 mg QD x 20 days | 14 | R(+) enantiomer: 0.99 [0.94, 1.04] S(-) enantiomer: 0.99 [0.95, 1.04] | R(+) enantiomer: 0.95 [0.87, 1.03] S(-) enantiomer: 0.99 [0.86, 1.05] | No change in warfarin INR No dose adjustment | ||||||
Digoxin (P-gp substrate) | 0.5 mg single dose | 40 mg QD x 11 days | 20 | 1.27 [1.12, 1.43] | 1.21 [1.05, 1.40] | Monitor digoxin concentrations | ||||||
Abbreviations: CI=confidence interval; AUC=area under the plasma concentration-time curve; Cmax=maximum observed concentration; QD= once-daily; EE=ethinyl estradiol; NGMN=norelgestromin, active metabolite of norgestimate; INR=international normalized ratio
Co-administration of CNS-active drugs
An additive effect on psychomotor performance was observed when a single dose of 40 mg of BELSOMRA® was co-administered with a single dose of 0.7 g/kg alcohol to healthy subjects (N=31). Suvorexant did not affect alcohol concentrations and alcohol did not affect suvorexant concentrations.
When a single dose of 40 mg of BELSOMRA® was co-administered with paroxetine 20 mg at steady state levels in healthy subjects, there were no significant changes in pharmacokinetic parameters of suvorexant, and no pharmacodynamic interaction was demonstrated in a psychomotor test.
8.3 Drug-Food Interactions
BELSOMRA® may be taken with or without food. However, for faster sleep onset, suvorexant should not be administered with or soon after a meal (see DOSAGE AND ADMINISTRATION, Dosing Considerations; ACTION AND CLINICAL PHARMACOLOGY, Pharmacokinetics, Absorption).
Grapefruit juice is an inhibitor of CYP3A, which may result in increased plasma concentrations of BELSOMRA® (See DOSAGE AND ADMINISTRATION, Recommended Dose and Dosage Adjustment, Use with CYP3A Inhibitors; DRUG INTERACTIONS, Effects of Other Drugs on BELSOMRA®, CYP3A Inhibitors).
9 ACTION AND CLINICAL PHARMACOLOGY
9.1 Mechanism of Action
Suvorexant is a highly selective reversible high affinity orexin receptor antagonist at OX1R (Ki 0.55 nM) and OX2R (Ki 0.35 nM) receptors.
The orexin neuropeptide signaling system is a central promoter of wakefulness. Orexin-producing neuronal cell bodies are localized specifically in the hypothalamus and project to the wakefulness mediating neurons of the brain. Suvorexant is thought to suppress wake drive by blocking the binding of the wake-promoting neuropeptides orexin A and orexin B to OX1R and OX2R reversibly.
Antagonism of orexin receptors may also underlie potential adverse effects such as signs of narcolepsy/cataplexy. Genetic mutations in the orexin system in animals result in hereditary narcolepsy; loss of orexin neurons has been reported in humans with narcolepsy.
Suvorexant has no direct pharmacological activity or binding affinity (Ki >10 uM) at gamma-aminobutyric acid (GABA), serotonin, dopamine, noradrenaline, melatonin, histamine, acetylcholine, or opiate receptors.
9.2 Pharmacodynamics
Evaluation of QTc Interval: The effects of suvorexant on QTc interval were evaluated in a randomized, placebo-, and active-controlled (moxifloxacin 400 mg) crossover study in healthy subjects (n=53). The upper bound of the one-sided 95% confidence interval for the largest placebo-adjusted, baseline-corrected QTc interval was below 10 ms based on analysis of suvorexant doses up to 240 mg. BELSOMRA® thus does not prolong the QTc interval to any clinically relevant extent.
Effects on Driving: Two randomized, double-blind, placebo- and active-controlled, four-period crossover studies evaluated the effects of nighttime administration of BELSOMRA® on next-morning driving performance 9 hours after dosing in 24 healthy elderly (≥65 years old, mean age 69 years; 14 men, 10 women) and 28 non-elderly (mean age 46 years; 13 men, 15 women) subjects.
The primary outcome measure was change in Standard Deviation of Lane Position (SDLP), a measure of driving performance, assessed using a symmetry analysis. Driving impairment was defined as a difference from placebo in SDLP of 2.4 cm, similar to the mean impairment resulting from blood alcohol concentrations of 0.5 g/L or more. The analysis showed clinically meaningful impaired driving performance in some subjects. This effect was observed in non-elderly subjects after one night of dosing with either 20 mg or 40 mg, and after eight nights of dosing with 40 mg of BELSOMRA®. A statistically significant effect was not observed in elderly subjects after both one night and eight nights of dosing with either 15 mg or 30 mg of BELSOMRA. Across these two studies, five subjects (4 non-elderly women on BELSOMRA; 1 elderly woman on placebo) prematurely stopped their driving tests due to somnolence. Due to individual variation, all patients should be advised not to drive, operate machinery or engage in other activities requiring full mental alertness until they experience how the drug affects them the next day (See WARNINGS AND PRECAUTIONS, General, CNS Depressant Effects and Daytime Impairment, including Driving Impairment).
Effects on Next-day Memory and Balance in Elderly and Non-elderly: The two studies designed to evaluate the effects of suvorexant in driving (see above) also evaluated memory and balance as secondary outcomes using word learning tests and body sway tests, respectively, at 11 hours after the evening dosing. In the trial in healthy non-elderly subjects, there was a significant decrease in word recall after the words were presented to subjects in the morning following a single dose of 40 mg BELSOMRA®, and there was a significant increase on body sway area in the morning following a single dose of 20 mg or 40 mg BELSOMRA®.
Middle of the Night Safety in Elderly Subjects: A double-blind, randomized, placebo-controlled trial evaluated the effect of a single dose of BELSOMRA® on balance, memory and psychomotor performance in healthy elderly subjects (n=12) after being awakened during the night. Nighttime dosing of BELSOMRA® 30 mg resulted in impairment of balance (measured by body sway area) at 90 minutes as compared to placebo.
Respiratory Safety:
Use in Healthy subjects with Normal Respiratory Function: A randomized, placebo-controlled, double-blind, crossover trial in healthy non-elderly subjects (n=12) evaluated the respiratory depressant effect of BELSOMRA® (40 mg and 150 mg) after one night of treatment. At the doses studied, BELSOMRA® had no respiratory depressant effect as measured by oxygen saturation (See WARNINGS AND PRECAUTIONS, General, Patients with Compromised Respiratory Function).
9.3 Pharmacokinetics
Suvorexant exposure increases in a less than strictly dose-proportional manner over the range of 10-80 mg due to decreased absorption at higher doses. Suvorexant pharmacokinetics are similar in healthy subjects and patients with insomnia.
Absorption: Suvorexant peak concentrations occur at a median tmax of 2 hours (range 30 minutes to 6 hours) under fasted conditions. The mean absolute bioavailability of 10 mg is 82%.
Ingestion of suvorexant with a high-fat meal resulted in no meaningful change in AUC or Cmax but a delay in tmax of approximately 1.5 hours. Suvorexant may be taken with or without food; however for faster sleep onset, suvorexant should not be administered with or soon after a meal.
Distribution: The mean volume of distribution of suvorexant is approximately 49 liters. Suvorexant is extensively bound (>99%) to human plasma proteins and does not preferentially distribute into red blood cells. Suvorexant binds to both human serum albumin and α1-acid glycoprotein.
Metabolism: Suvorexant is mainly eliminated by metabolism, primarily by CYP3A with a minor contribution from CYP2C19. The major circulating entities are suvorexant and a hydroxy-suvorexant metabolite. This metabolite is not expected to be pharmacologically active.
Elimination: The primary route of elimination is through the feces, with approximately 66% of radiolabeled dose recovered in the feces compared to 23% in the urine. The systemic pharmacokinetics of suvorexant are linear with an accumulation of approximately 1- to 2-fold with once-daily dosing. Steady-state is achieved by 3 days. The mean t1/2 is approximately 12 hours (95% CI: 12 to 13).
Special Populations and Conditions
Geriatrics (≥ 65 years of age): The confirmatory safety and efficacy studies for suvorexant were designed with lower doses for elderly (15 mg) compared to non-elderly patients (20 mg), which resulted in similar exposures in both populations. However, dosage adjustments in geriatrics are not generally necessary, and the initial dose is 10 mg for both elderly and non-elderly patients (See DOSAGE AND ADMINISTRATION, Geriatrics).
Hepatic Insufficiency: Suvorexant exposure after a single dose was similar in patients with moderate hepatic impairment (Child-Pugh category 7 to 9) and healthy matched control subjects; however, the suvorexant apparent terminal half-life was increased from approximately 15 hours (range 10 - 22 hours) in healthy subjects to approximately 19 hours (range 11 - 49 hours) in patients with moderate hepatic impairment (See DOSAGE AND ADMINISTRATION, Recommended Dose and Dosage Adjustment, Patients with Hepatic Impairment; WARNINGS AND PRECAUTIONS, Hepatic/Biliary/Pancreatic, Patients with Severe Hepatic Impairment).
Renal Insufficiency: Suvorexant exposure (expressed as total and unbound concentrations) was similar between patients with severe renal impairment (urinary creatinine clearance ≤30 mL/min/1.73m2) and healthy matched control subjects. No dose adjustment is required in patients with renal impairment (See DOSAGE AND ADMINISTRATION, Recommended Dose and Dosage Adjustment, Patients with Renal Impairment).
Population Pharmacokinetic Analysis: Gender, age, body mass index (BMI), and race were included as factors assessed in the population pharmacokinetic model to evaluate suvorexant pharmacokinetics in healthy subjects and to predict exposures in the patient population. Age and race are not predicted to have any clinically meaningful changes on suvorexant pharmacokinetics; therefore, no dose adjustment is warranted based upon these factors.
Suvorexant exposure is higher in females than in males. In females, the AUC and Cmax are increased by 17% and 9%, respectively, following administration of BELSOMRA® 40 mg. The average concentration of suvorexant 9 hours after dosing is 5% higher for females across the dose range studied (10-40 mg). Dose adjustment of BELSOMRA® is generally not needed based on gender only.
Apparent oral clearance of suvorexant is inversely related to body mass index. In obese patients, the AUC and Cmax are increased by 31% and 17%, respectively. The average concentration of suvorexant approximately 9 hours after a 20 mg dose is 15% higher in obese patients (BMI > 30 kg/m2) relative to those with a normal BMI (BMI ≤ 25 kg/m2).
In obese females, the AUC and Cmax are increased by 46% and 25%, respectively, compared to non-obese females. The higher exposure to suvorexant in obese females should be considered before increasing dose (See DOSAGE AND ADMINISTRATION, Special Populations).
10 STORAGE, STABILITY AND DISPOSAL
Store at room temperature, 15°C - 30°C.
Store in the original package until use, to protect from light and moisture.
PART II: SCIENTIFIC INFORMATION
11 PHARMACEUTICAL INFORMATION
Drug Substance
Proper name: suvorexant
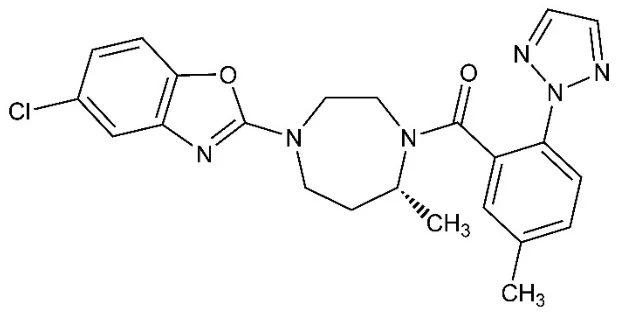
Chemical name: [(7R)-4-(5-chloro-2-benzoxazolyl)hexahydro-7-methyl-1H-1,4-diazepin-1-yl][5-methyl-2-(2H-1,2,3-triazol-2-yl)phenyl]methanone
Molecular formula and: C23H23ClN6O2
molecular mass: 450.921
Structural formula:
Physicochemical properties: Suvorexant is a white to off-white powder that is insoluble in water
12 CLINICAL TRIALS
12.1 Trial Design and Study Demographics
Table 5- Summary of patient demographics for clinical trials in specific indication
| Study # | Trial design | Dosage, route of administration and duration | Study subjects (n=number) | Mean age (Range) | Gender | ||||
Study 1 Pivotal Efficacy 1 (PN028) | Phase 3, multicenter, randomized, double-blind, placebo-controlled, parallel group, trial | Suvorexant HD
Suvorexant LD
Placebo 3-month Treatment Phase followed by 3-month Extension Phase | Treatment Phase (PN028) Total: 1021
Completed: 916 Extension Phase Total: 423
Completed: 377 | 56 (18-87) 58% were non-elderly (<65 years) and 42% were elderly (≥65 years) | 38% Male and 62% Female | ||||
Study 2 Pivotal Efficacy 2 (PN029) | Phase 3, multicenter, randomized, double-blind, placebo-controlled, parallel group trial | Suvorexant HD
Suvorexant LD
Placebo 3-month Treatment Phase | Treatment Phase (PN029) Total: 1009
Completed: 881 | 56 (18-86) 59% were non-elderly (<65 years) and 41% were elderly (≥65 years) | 33% Male and 67% Female | ||||
Study 3 1 month cross-over study (PN006) | Phase 2, randomized, double-blind, placebo-controlled, 2-period (4 weeks per period) crossover trial | Suvorexant
|
| 44 (18-64) | 42% Male and 58% Female | ||||
| HD= high dose, LD= low dose, PBO= placebo | |||||||||
12.2 Study Results
Controlled Clinical Studies
BELSOMRA® was evaluated in three clinical trials in patients with insomnia characterized by difficulties with sleep onset and/or sleep maintenance.
Two similarly designed, 3-month, randomized, double-blind, placebo-controlled, parallel-group studies were conducted (Studies 1 and 2). In both studies, non-elderly (age 18-64) and elderly (age ≥ 65) patients were randomized separately. For the studies together, non-elderly adults (mean age 46 years; 465 females, 275 males) were treated with BELSOMRA® 20 mg (n=291) or placebo (n=449). Elderly patients (mean age 71 years, 346 females, 174 males) were treated with BELSOMRA® 15 mg (n=202) or placebo (n=318). Twenty seven percent of patients treated with BELSOMRA® 15 mg or 20 mg in Study 1 and Study 2 were non-Caucasians. The majority (69%) of the non-Caucasian patients was Asian.
In Study 1 and Study 2, BELSOMRA® 15 mg or 20 mg was superior to placebo for sleep latency as assessed both objectively by polysomnography (Table 6) and subjectively by patient-estimated sleep latency (Table 7). BELSOMRA® 15 mg or 20 mg was also superior to placebo for sleep maintenance, as assessed both objectively by polysomnography (Table 8) and subjectively by patient-estimated total sleep time (Table 9).
Table 6: Polysomnographic (PSG) Assessment of Sleep Onset (Latency to Persistent Sleep, LPS) in Studies 1 and 2
Mean Baseline and Change from Baseline† LPS After 1 Night and 1 and 3 Months [minutes] | Difference (and 95% Confidence Interval)† Between Suvorexant and Placebo [minutes] | ||||||||||||||
|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|
| Study 1 | |||||||||||||||
Placebo (n=290) | Suvorexant 15-20 mg‡ (n=193) | ||||||||||||||
| Baseline | 66 | 69 | |||||||||||||
| n | Change | n | Change | Change | |||||||||||
| Night 1 | 290 |
| 193 |
|
| ( - 15, - 4 ) | |||||||||
| Month 1 | 272 |
| 185 |
|
| ( - 16, - 5 ) | |||||||||
| Month 3 | 251 |
| 172 |
|
| ( - 14, - 2 ) | |||||||||
| Study 2 | |||||||||||||||
Placebo (n=286) | Suvorexant 15-20 mg‡ (n=145) | ||||||||||||||
| Baseline | 69 | 65 | |||||||||||||
| n | Change | n | Change | Change | |||||||||||
| Night 1 | 284 |
| 144 |
|
| ( - 21, - 4 ) | |||||||||
| Month 1 | 271 |
| 133 |
|
| ( - 15, - 1 ) | |||||||||
| Month 3 | 255 |
| 127 |
| 0 | ( - 8, 8 ) | |||||||||
† Change from baseline, treatment differences, and 95% confidence intervals based upon estimated means; mean baseline is from patients with Night 1 data ‡ 15 mg in elderly and 20 mg in non-elderly patients * Nominal p<0.05; **p<0.01; ***p<0.001 | |||||||||||||||
& Significant as per multiplicity testing procedure for Study 1 (these treatment comparisons were not part of the multiplicity testing procedure for Study 2)
Table 7: Patient-estimated Sleep Onset (Subjective Time to Sleep Onset, sTSO) in Studies 1 and 2
Mean Baseline and Change from Baseline† sTSO After 1 Week and 1 and 3 Months [minutes] | Difference (and 95% Confidence Interval)† Between Suvorexant and Placebo [minutes] | ||||||||||||||||
|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|
| Study 1 | |||||||||||||||||
Placebo (n=382) | Suvorexant 15-20 mg‡ (n=251) | ||||||||||||||||
| Baseline | 67 | 64 | |||||||||||||||
| n | Change | n | Change | Change | |||||||||||||
| Week 1 | 376 |
| 248 |
|
| ( - 10, - 1 ) | |||||||||||
| Month 1 | 365 |
| 244 |
|
| ( - 11, 0 ) | |||||||||||
| Month 3 | 339 |
| 228 |
|
| ( - 10, 0 ) | |||||||||||
| Study 2 | |||||||||||||||||
Placebo (n=369) | Suvorexant 15-20 mg‡ (n=231) | ||||||||||||||||
| Baseline | 83 | 86 | |||||||||||||||
| n | Change | n | Change | Change | |||||||||||||
| Week 1 | 364 |
| 231 |
|
| ( - 13, - 2 ) | |||||||||||
| Month 1 | 350 |
| 219 |
|
| ( - 14, 0 ) | |||||||||||
| Month 3 | 325 |
| 197 |
|
| ( - 15, 0 ) | |||||||||||
† Change from baseline, treatment differences, and 95% confidence intervals based upon estimated means; mean baseline is from patients with Week 1 data ‡ 15 mg in elderly and 20 mg in non-elderly patients * Nominal p<0.05; **p<0.01; ***p<0.001 | |||||||||||||||||
& Significant as per multiplicity testing procedure for Study 1 (these treatment comparisons were not part of the multiplicity testing procedure for Study 2)
Table 8: Polysomnographic (PSG) Assessment of Sleep Maintenance (Wake After Sleep Onset, WASO) in Studies 1 and 2
Mean Baseline and Change from Baseline† WASO After 1 Night and 1 and 3 Months [minutes] | Difference (and 95% Confidence Interval)† Between Suvorexant and Placebo [minutes] | ||||||||||||||
|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|
| Study 1 | |||||||||||||||
Placebo (n=290) | Suvorexant 15-20 mg‡ (n=193) | ||||||||||||||
| Baseline | 115 | 120 | |||||||||||||
| n | Change | n | Change | Change | |||||||||||
| Night 1 | 287 |
| 192 |
|
| ( - 39, - 26 ) | |||||||||
| Month 1 | 272 |
| 185 |
|
| ( - 34, - 18 ) | |||||||||
| Month 3 | 251 |
| 172 |
|
| ( - 25, - 8 ) | |||||||||
| Study 2 | |||||||||||||||
Placebo (n=286) | Suvorexant 15-20 mg‡ (n=145) | ||||||||||||||
| Baseline | 118 | 119 | |||||||||||||
| n | Change | n | Change | Change | |||||||||||
| Night 1 | 283 |
| 144 |
|
| ( - 45, - 29 ) | |||||||||
| Month 1 | 270 |
| 132 |
|
| ( - 33, - 15 ) | |||||||||
| Month 3 | 252 |
| 127 |
|
| ( - 40, - 22 ) | |||||||||
† Change from baseline, treatment differences, and 95% confidence intervals based upon estimated means; mean baseline is from patients with Night 1 data ‡ 15 mg in elderly and 20 mg in non-elderly patients * Nominal p<0.05; **p<0.01; ***p<0.001 & Significant as per multiplicity testing procedure for Study 1 (these treatment comparisons were not part of the multiplicity testing procedure for Study 2) | |||||||||||||||
Table 9: Patient-estimated Sleep Time (Subjective Total Sleep Time, sTST) in Studies 1 and 2
Mean Baseline from Baseline† sTST After 1 Week and 1 and 3 Months [minutes] | Difference (and 95% Confidence Interval)† Between Suvorexant and Placebo [minutes] | |||||||||||||||
|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|
| Study 1 | ||||||||||||||||
Placebo (n=382) | Suvorexant 15-20 mg‡ (n=251) | |||||||||||||||
| Baseline | 315 | 322 | ||||||||||||||
| n | Change | n | Change | Change | ||||||||||||
| Week 1 | 376 | 15 | 248 | 28 | 14***, & | ( 7, 20 ) | ||||||||||
| Month 1 | 365 | 23 | 244 | 39 | 16***, & | ( 8, 25 ) | ||||||||||
| Month 3 | 339 | 41 | 228 | 51 | 11*, & | ( 2, 20 ) | ||||||||||
| Study 2 | ||||||||||||||||
Placebo (n=369) | Suvorexant 15-20 mg‡ (n=231) | |||||||||||||||
| Baseline | 307 | 299 | ||||||||||||||
| n | Change | n | Change | Change | ||||||||||||
| Week 1 | 364 | 14 | 231 | 31 | 17*** | ( 9, 25 ) | ||||||||||
| Month 1 | 350 | 22 | 219 | 43 | 21*** | ( 12, 30 ) | ||||||||||
| Month 3 | 325 | 38 | 197 | 60 | 22*** | ( 12, 33 ) | ||||||||||
† Change from baseline, treatment differences, and 95% confidence intervals based upon estimated means; mean baseline is from patients with Week 1 data ‡ 15 mg in elderly and 20 mg in non-elderly patients * Nominal p<0.05; **p<0.01; ***p<0.001 & Significant as per multiplicity testing procedure for Study 1 (these treatment comparisons were not part of the multiplicity testing procedures for Study 2) | ||||||||||||||||
In a 1-month crossover study (Study 3), non-elderly adults (age 18-64 years, mean age 44 years) were treated with placebo (n=249) and BELSOMRA® at a dose of 10 mg (n=62). BELSOMRA® 10 mg was superior to placebo for sleep efficiency and total sleep time, as assessed objectively by polysomnography.
BELSOMRA® was also evaluated at doses of 30 mg and 40 mg in the 3-month placebo-controlled trials (Study 1 and Study 2). The higher doses were associated with significantly more adverse effects and an unfavourable risk-benefit balance.
13 NON-CLINICAL TOXICOLOGY
Acute Toxicity
No single-dose toxicity studies have been conducted. In multiple dose studies, mortality was not observed in rats or dogs after the first dose at systemic exposures 88-times and 59-times, respectively, the clinical exposure at the Maximum Recommended Human Dose (MRHD) (20 mg).
Chronic Toxicity
In long-term rat studies, findings consisted of minor clinical pathology changes and histomorphologic alterations in the liver, thyroid, pancreas, and stomach. Hepatocellular and thyroid follicular cell hypertrophy were findings consistent with microsomal enzyme induction and are well described to be rodent-specific. Chronic inflammation in the pancreas in male rats resembled the age-related pancreatic change noted in older rats, and erosion of the glandular mucosa in the stomach was considered to be a local toxicity of the test article or formulation. No adverse effects were observed in rats at exposures 19- to 23-times the clinical exposure at the MRHD (20 mg).
In the 2-year carcinogenicity study in rats, an increased incidence of retinal atrophy was observed at all doses. Plasma AUCs at the lowest dose tested were approximately 7 times that in humans at the MRHD. In subsequent studies of suvorexant in albino and pigmented rats, retinal atrophy was delayed in onset and, after approximately one year of dosing, was of lower incidence and severity in pigmented rats.
In long-term dog studies, adverse clinical pathology changes were limited to dose-related increases in alkaline phosphatase, and histomorphologic findings were limited to hepatocellular hypertrophy that was not considered adverse. Toxicity was not observed in dogs at exposures 45-times the clinical exposure at the MRHD (20mg).
In dogs, daily oral administration of suvorexant (5, 30 mg/kg) for 4-7 days resulted in behaviour characteristic of cataplexy (e.g., transient limb buckling, prone posture) when presented with food enrichment, a stimulus demonstrated to induce cataplexy in dogs with hereditary narcolepsy.
Carcinogenesis
No evidence of carcinogenic potential was observed in hemizygous Tg.rasH2 mice dosed orally for 6 months at exposures up to 105-times the clinical exposure at the MRHD (20mg).
In the 2-year carcinogenicity study in rats, there was an increased incidence of hepatic and thyroid follicular cell adenomas. These changes were secondary to hepatic enzyme induction and increased TSH production, respectively, which are mechanisms believed to be rodent-specific. At the no-effect dose for tumors, exposure was 7-times the clinical exposure at the MRHD (20 mg).
Mutagenesis
Suvorexant was negative in in vitro (bacterial reverse mutation, alkaline elution, and chromosomal aberration) and in vivo (rat and mouse micronucleus) genetic toxicology assays.
Reproduction
In male and female rats treated prior to and during mating and early gestation, decreases were observed in corpora lutea, implantations, and resultant live fetuses. There were no effects in males. At the no-effect dose, exposure was approximately 20-times the clinical exposure at the MRHD (20 mg).
Development
Teratogenicity was not observed in pregnant rats or rabbits treated during the period of organogenesis. In rats, developmental toxicity was limited to a decrease in fetal body weights. In rabbits, there was no evidence of developmental toxicity. The maternal exposure in rats and rabbits at the no-effect dose was 25-times and 39-times the clinical exposure at the MRHD (20 mg), respectively.
Following oral administration to rats throughout gestation and lactation, effects in the offspring were limited to a transient decrease in body weight at the highest dose tested. The maternal exposure at the no-effect dose was 25-times the clinical exposure at the MRHD (20 mg).