


Product Monograph - Brevibloc Injection 10mg/mL
SUMMARY PRODUCT INFORMATION
| Route of Administration | Dosage Form / Strength | Nonmedicinal Ingredients |
| Intravenous Injection | Solution / 10 mg/mL (100 mg/10 mL vials) | Glacial Acetic Acid USP, Hydrochloric Acid NF, Sodium Acetate Trihydrate USP, Sodium Chloride USP, Sodium Hydroxide, Water for Injection USP |
| Intravenous Injection | Solution / 10 mg/mL (2500 mg/250 mL bags) | |
INDICATIONS AND CLINICAL USE
BREVIBLOC Injection / BREVIBLOC PREMIXED Injection (esmolol hydrochloride) is indicated for:
- the perioperative management of tachycardia and hypertension in patients in whom there is a concern for compromised myocardial oxygen balance and who, in the judgement of the physician, are clearly at risk of developing haemodynamically-induced myocardial ischemia.
- the rapid control of ventricular rate in patients with atrial fibrillation or atrial flutter in acute situations when the use of a short-acting agent is desirable.
BREVIBLOC Injection / BREVIBLOC PREMIXED Injection is for short-term use only (up to 24 hours) and is not indicated for use in chronic settings.
Geriatrics (≥ 65 years of age): The safety and effectiveness of BREVIBLOC (esmolol hydrochloride) products in elders have not been established.
Pediatrics (< 18 years of age): The safety and effectiveness of BREVIBLOC (esmolol hydrochloride) products in children have not been established.
CONTRAINDICATIONS
BREVIBLOC Injection / BREVIBLOC PREMIXED Injection (esmolol hydrochloride) is contraindicated in patients who require inotropic agents and/or vasopressors to maintain systemic blood pressure and cardiac output.
IV administration of cardiodepressant calcium-channel antagonists (e.g., verapamil, diltiazem) and BREVIBLOC products should not be used within 24 hours (i.e., while cardiac effects from the other are still present); fatal cardiac arrests have occurred in patients receiving BREVIBLOC products and intravenous verapamil.
BREVIBLOC Injection / BREVIBLOC PREMIXED Injection is also contraindicated in patients with:
- Hypotension
- Sinus bradycardia
- Sick sinus syndrome
- Second and third degree A-V block
- Pulmonary hypertension
- Right ventricular failure secondary to pulmonary hypertension
- Decompensated heart failure
- Cardiogenic shock (see WARNINGS)
- Nontreated pheochromocytoma
- Known hypersensitivity to esmolol or any of the inactive ingredients of the product (cross-sensitivity between beta blockers is possible)
WARNINGS AND PRECAUTIONS
General
Abrupt Cessation of Therapy with BREVIBLOC (esmolol hydrochloride) products:
Abrupt cessation of BREVIBLOC Injection / BREVIBLOC PREMIXED Injection in patients has not been reported to produce the withdrawal effects which may occur with abrupt withdrawal of beta-blockers following chronic use in coronary artery disease patients. However, caution should be used in discontinuing BREVIBLOC (esmolol hydrochloride) infusions abruptly in these patients.
Serious Warnings and Precautions
DURING THE ADMINISTRATION OF BREVIBLOC INJECTION / BREVIBLOC PREMIXED INJECTION (esmolol hydrochloride) PATIENTS SHOULD BE CAREFULLY MONITORED, WITH PARTICULAR ATTENTION TO HEART RATE AND BLOOD PRESSURE
In a clinical electrophysiology study, the heart rate 30 minutes after BREVIBLOC product discontinuation was modestly but significantly higher than at baseline.
Beta blockers also increase the risk of clonidine-, guanfacine-, and moxonidine-withdrawal rebound hypertension. If antihypertensive therapy needs to be interrupted or discontinued, the beta blocker should always be the first medication to be discontinued and the discontinuation should be gradual. (See DRUG INTERACTIONS)
Patients with hypothermia:
BREVIBLOC products should be used with caution in patients who are being treated for hypertension, where the increased blood pressure is primarily due to vasoconstriction associated with hypothermia.
Infusion site reactions:
Infusion site reactions have occurred with the use of BREVIBLOC products. They include signs and symptoms of infusion site irritation and inflammation but also severe reactions (thrombophlebitis, necrosis, and blistering), in particular when associated with extravasation (See ADVERSE REACTIONS). Infusions into small veins or through a butterfly catheter should be avoided.
If a local infusion site reaction develops, an alternative infusion site should be used.
Use in patients with metabolic acidosis:
Beta blockers, including BREVIBLOC products, have been reported to cause, or contribute to the development of, hyperkalemic renal tubular acidosis. Furthermore, acidosis in general may be associated with reduced cardiac contractility. BREVIBLOC products should be used with caution in patients with preexistent metabolic acidosis.
Cardiovascular
Cardiovascular adverse reactions to beta blockers, including BREVIBLOC products, can be severe, in particular in hemodynamically compromised patients and patients taking medications that increase the risk of cardiovascular reactions (See DRUG INTERACTIONS). Severe reactions may include loss of consciousness, cardiogenic shock, cardiac arrest, and can be fatal.
BREVIBLOC products should not be used to control tachycardia in patients receiving drugs that are vasoconstrictive and have positive inotropic effects, such as epinephrine, norepinephrine and dopamine, because of the risk of reducing cardiac contractility in the presence of high systemic vascular resistance.
BREVIBLOC products, if not contraindicated (See CONTRAINDICATIONS), should be used with caution and only after careful individual assessment of the risks and expected benefit in hemodynamically compromised patients and in patients at increased risk due to possible drug-drug interactions.
The administration of BREVIBLOC Injection / BREVIBLOC PREMIXED Injection has been associated with excessive hypotension. The hypotensive effect of BREVIBLOC Injection / BREVIBLOC PREMIXED Injection is dose related, but can occur at any dose, and may increase in the presence of both narcotic analgesics and inhalational anesthetics. In patients with a propensity to develop hypotension (e.g., hypovolemic patients), BREVIBLOC (esmolol hydrochloride) products should be used with special caution, and close monitoring and only when in the physician's judgement the potential benefits outweigh the risk. In the event of hypotension, BREVIBLOC Injection / BREVIBLOC PREMIXED Injection should be discontinued or reduced.
Hypotension typically disappears within 30 minutes after discontinuation of the administration of BREVIBLOC products. In some cases, additional interventions may be necessary.
Cardiac Failure:
Sympathetic stimulation is a vital component supporting circulatory function in patients with congestive heart failure. Inhibition with beta-blockade always carries the potential hazard of further depressing myocardial contractility and may precipitate or worsen cardiac failure. Therefore, special caution should be exercised when administering BREVIBLOC Injection / BREVIBLOC PREMIXED Injection to patients with a history of heart failure. Beta-blockers act selectively without abolishing the inotropic action of digitalis on the heart muscle. The effects of beta-blockers and digitalis are additive in depressing A-V nodal conduction. Even in patients with no history of cardiac failure, continued depression of the myocardium over a period of time can, in some cases, lead to cardiac failure. Therefore, at the first sign or symptom of impending cardiac failure, the dosage of BREVIBLOC (esmolol hydrochloride) products should be reduced or the drug should be withdrawn. Because of the short elimination half-life of BREVIBLOC (esmolol hydrochloride) products, these measures may be sufficient but specific treatment may also be considered.
Beta blockers affect sinus node function and sinoatrial and atrioventricular conduction, and carry the risk of sinus pause and sinoatrial and atrioventricular block, including complete block, which can lead to cardiac arrest. This effect is particularly relevant in patients with preexisting sinus node dysfunction and conduction disorders.
BREVIBLOC products should be used with caution in patients with other cardiac conduction disturbances, including first-degree atrioventricular block.
Use in patients with Prinzmetal’s angina:
Beta blockers may exacerbate anginal attacks in patients with Prinzmetal’s angina due to unopposed alpha-receptor–mediated coronary artery vasoconstriction. Nonselective beta blockers should not be used for these patients, and beta-1 selective blockers should be used only with caution.
Endocrine and Metabolism
Diabetes Mellitus/Hypoglycaemia:
BREVIBLOC Injection / BREVIBLOC PREMIXED Injection should be administered with caution to patients subject to or prone to hypoglycaemia, or to diabetic patients (especially those with labile diabetes) who are receiving insulin or oral hypoglycaemic agents. Beta-adrenergic blockers may mask tachycardia occurring with hypoglycemia, but other manifestations such as dizziness and sweating may not be masked.
Beta blockers can increase the blood-glucose lowering effect of antidiabetic agents. (See DRUG INTERACTIONS)
Use in patients with pheochromocytoma:
BREVIBLOC products should be used with caution and only after pretreatment with alpha-receptor blockers in patients with pheochromocytoma. (See CONTRAINDICATIONS)
Hyperkalemia:
Beta blockers, including BREVIBLOC products, have been associated with increases in serum potassium levels and hyperkalemia. The risk is increased in patients with risk factors such as renal impairment. Intravenous administration of beta blockers has been reported to cause potentially life-threatening hyperkalemia in hemodialysis patients.
Use in patients with hyperthyroidism:
Beta-adrenergic blockade may mask certain clinical signs (e.g., tachycardia) of hyperthyroidism. Abrupt withdrawal of beta blockade might precipitate a thyroid storm; therefore, patients suspected of developing thyrotoxicosis from whom beta blocking therapy is to be withdrawn, should be monitored closely.
Hematologic
Use in hypovolemic patients:
In hypovolemic patients, BREVIBLOC products can attenuate reflex tachycardia and increase the risk of hypotension. Therefore, BREVIBLOC products should be used with caution in such patients.
Use in patients with peripheral circulatory disorders:
In patients with peripheral circulatory disorders (including Raynaud’s disease or syndrome, and peripheral occlusive vascular disease), BREVIBLOC products should be used with caution as beta blockers may aggravate peripheral circulatory disorders.
Hepatic/Biliary/Pancreatic
No special precautions are necessary in patients with hepatic impairment because BREVIBLOC products are metabolized by red-blood cell esterases.
Immune
Use in patients at risk of severe acute hypersensitivity reactions:
When using beta blockers, patients at risk of anaphylactic reactions may be more reactive to allergen exposure (accidental, diagnostic, or therapeutic).
Patients using beta blockers may be unresponsive to the usual doses of epinephrine used to treat anaphylactic or anaphylactoid reactions. (See DRUG INTERACTIONS)
Use in patients with a personal or family history of psoriasis:
Beta blockers have been associated with the development of psoriasis or psoriasiform eruptions and with aggravation of psoriasis.
Patients with a personal or family history of psoriasis should be administered beta blockers only after careful consideration of expected benefits and risks.
Neurologic
Use in patients with myasthenia gravis:
Beta blockers, including BREVIBLOC products, have caused muscle weakness. BREVIBLOC products should be used with caution in patients with myasthenia gravis.
Renal
Renal Impairment:
The pharmacokinetics of BREVIBLOC Injection / BREVIBLOC PREMIXED Injection (esmolol hydrochloride) are unchanged in kidney-impaired patients except that the volume of distribution is increased. However, the acid metabolite of BREVIBLOC (esmolol hydrochloride) products is primarily excreted unchanged by the kidney, and its excretion is significantly decreased in patients with renal disease. Thus BREVIBLOC Injection / BREVIBLOC PREMIXED Injection should be administered with caution to patients with impaired renal function. The elimination half-life of the acid metabolite was prolonged ten-fold and the plasma level was considerably elevated in patients with end-stage renal disease.
Respiratory
Bronchospastic Diseases:
Patients with bronchospastic diseases should not, in general, receive beta-blockers. Because of its relative beta-1 selectivity and titratability, BREVIBLOC Injection / BREVIBLOC PREMIXED Injection may be used with caution in patients with bronchospastic diseases. Since beta-1 selectivity is not absolute, BREVIBLOC (esmolol hydrochloride) products should be carefully titrated to obtain the lowest possible effective dose. In the event of bronchospasm, the infusion should be terminated immediately and a beta-2 stimulating agent may be administered if conditions warrant.
Special Populations
Pregnant Women: There are no studies in pregnant women. BREVIBLOC (esmolol hydrochloride) products should be used during pregnancy only if the potential benefit justifies the potential risk to the fetus.
If treatment is considered, the uteroplacental blood flow should be monitored because beta blockers may reduce placental perfusion.
Use of BREVIBLOC products in the second or third trimester of pregnancy or during labor or delivery has been reported to cause fetal bradycardia, which continued after termination of drug infusion. When pregnant women are treated shortly before delivery, the beta-blocking action can persist in the newborn for several days after birth and may result in clinically relevant bradycardia, respiratory distress, hypoglycemia, and hypotension. Reduced compensatory cardiovascular reactions and heart failure may, however, require hospitalization in intensive care. Newborns should be monitored accordingly.
Nursing Women: It is not known whether BREVIBLOC (esmolol hydrochloride) products are excreted in human milk. Caution, however, should be exercised when BREVIBLOC Injection / BREVIBLOC PREMIXED Injection is administered to a nursing mother.
Pediatrics: The safety and effectiveness of BREVIBLOC (esmolol hydrochloride) products in children have not been established.
Geriatrics: The safety and effectiveness of BREVIBLOC (esmolol hydrochloride) products in elders have not been established.
Monitoring and Laboratory Tests
During the administration of BREVIBLOC (esmolol hydrochloride) products patients should be carefully monitored, with particular attention to heart rate and blood pressure.
ADVERSE REACTIONS
Adverse Drug Reaction Overview
The most serious reported adverse reactions from clinical trial are hypotension, bradycardia, pulmonary edema, bronchospasm and administration site reactions some serious in nature. (See WARNINGS AND PRECAUTIONS)
The most frequent adverse drug reaction observed in clinical trials was hypotension, with asymptomatic hypotension being more common than symptomatic hypotension. Hypotension was resolved by dose reduction or discontinuation.
All of the Adverse Drug Reactions listed below may result in the need for clinical diagnosis or treatment.
Clinical Trial Adverse Drug Reactions
Because clinical trials are conducted under very specific conditions the adverse reaction rates observed in the clinical trials may not reflect the rates observed in practice and should not be compared to the rates in the clinical trials of another drug. Adverse drug reaction information from clinical trials is useful for identifying drug-related adverse events and for approximating rates.
The adverse reactions presented in this section have been identified in clinical trials with BREVIBLOC products. Some have been observed during the treatment of supraventricular tachycardia/tachyarrhythmia and in the perioperative setting. Others have been conducted in healthy volunteers. Multi-center and single-site, randomized, single-blind, double-blind, cross-over, and open label design trials were conducted with either a placebo or active comparator.
During Management of Perioperative Tachycardia and Associated Hypertension:
In clinical trials 763 patients were treated with BREVIBLOC (esmolol hydrochloride) Injection in operative settings.
BREVIBLOC Injection as a bolus of 100 mg and 200 mg was given in a total of 367 patients during clinical studies. Hypotension was reported in 16% among esmolol treated patients compared to 8% in the placebo group (187 patients).
When BREVIBLOC (esmolol hydrochloride) Injection was infused in 396 patients, hypotension was the most commonly observed side effect in 5% of patients.
A summary of the adverse effects, grouped by system, are:
Clinical Trial Adverse Reactions During Management of Perioperative Tachycardia and Associated Hypertension | |||
| BREVIBLOC 100 mg and 200 mg Bolus Dosing | |||
| System Organ Class (SOC) | Preferred MedDRA Term | BREVIBLOC Frequency (%) n = 367 | Placebo Frequency (%) n = 187 |
| Cardiac Disorders | Bradycardia | 4% | 4% |
| Vascular Disorders | Hypotension | 16% | 8% |
| BREVIBLOC Infusion | |||
| System Organ Class (SOC) | Preferred MedDRA Term | BREVIBLOC Frequency (%) n = 396 | |
| Cardiac Disorders | Bradycardia | 1% | |
| Vascular Disorders | Hypotension | 5% | |
None of these side effects were judged to be severe, and all resolved after the discontinuation of BREVIBLOC (esmolol hydrochloride) products.
During Management of Atrial Fibrillation and Atrial Flutter:
Most adverse effects reported in clinical trials with BREVIBLOC Injection in 390 patients with atrial fibrillation and atrial flutter have been mild and transient. The most serious adverse reaction observed was symptomatic hypotension (12%). BREVIBLOC (esmolol hydrochloride) Injection was discontinued in about 11% of the patients. Other adverse reactions, grouped by system, are:
Clinical Trial Adverse Reactions During Management of Atrial Fibrillation and Atrial Flutter | ||
| System Organ Class (SOC) | Preferred MedDRA Term | Frequency (%) n = 390 |
| Cardiac Disorders | Premature Ventricular Contraction | 1% |
| Accelerated idioventricular rhythm | --* | |
| Gastrointestinal Disorders | Nausea | 6% |
| Vomiting | 1% | |
| General Disorders and Administration Site Conditions | Hyperhidrosis | 9% |
| Administration site reactions (overall)1, 2 | 6% | |
| Administration site induration | 2% | |
| Administration site inflammation | 2% | |
| Infusion site extravasation | 2% | |
| Administration site erythema1 | 1% | |
| Administration site phlebitis and thrombophlebitis | --* | |
| Metabolism and Nutrition Disorders | Hyperkalemia | --* |
| Nervous System Disorders | Headache | 3% |
| Dizziness | 3% | |
| Somnolence | 3% | |
| Confusional state | 2% | |
| Agitation | 2% | |
| Fatigue | 1% | |
| Respiratory, Thoracic, and Mediastinal Disorders | Dyspnea | 1% |
| Vascular Disorders | Hypotension Asymptomatic hypotension | 25% |
| Symptomatic hypotension (hyperhidrosis, dizziness) | 12% | |
1 This frequency estimate is based on pooled supraventricular tachycardia/tachyarrhythmia studies involving 417 patients. 2 See injection site necrosis and blistering in Post-Market Adverse Drug Reactions section, and see statement in WARNINGS AND PRECAUTIONS, General, Infusion site reactions section. * Data not sufficient to establish frequency. | ||
Costochondritis and dysgeusia have been reported in a healthy volunteer study.
Less Common Clinical Trial Adverse Drug Reactions (<1%)
The following clinical trial adverse drug reactions are listed by MedDRA System Organ Class (SOC), then by Preferred Term in order of severity.
| During Management of Perioperative Tachycardia and Associated Hypertension | |
| Cardiac Disorders | myocardial ischemia, S-T segment depression, atrial fibrillation, nodal rhythm, ECG changes, hypertension |
| Gastrointestinal Disorders | vomiting, nausea |
| General Disorders and Administration Site Disorders | urticaria, pain at injection |
| Nervous System Disorders | agitation |
| Respiratory, Thoracic, and Mediastinal Disorders | bronchospasm, wheezing |
| During Management of Atrial Fibrillation and Atrial Flutter | |
| Cardiac Disorders | cardiac failure, pulmonary edema, chest pain, angina pectoris, bradycardia (< 50 beats per minute), atrioventricular block, nodal rhythm, pulmonary arterial pressure increased, recurrence of SVT, narrowed pulse pressure, ventricular ectopy, ventricular extrasystoles1, abnormal ECG |
| Eye Disorders | visual impairment |
| Gastrointestinal Disorders | abdominal pain2, constipation, dyspepsia, dry mouth |
| General Disorders and Administration Site Disorders | administration site burning, administration site edema, administration site ecchymosis, administration site erythema, enlarged macular area, asthenia, pyrexia, chills, cold sweat |
| Metabolism and Nutritional Disorders | anorexia |
| Musculoskeletal and Connective Tissue Disorders | musculoskeletal pain (midscapular pain) |
| Nervous System Disorders | syncope, convulsion, speech disorder, somnolence, paraesthesia, weakness |
| Psychiatric Disorders | depression, abnormal thinking, anxiety, irritability |
| Renal and Urinary Disorders | dysuria, urinary retention, oliguria |
| Respiratory, Thoracic, and Mediastinal Disorders | bronchospasm, pleural pain, pleural effusion, dyspnea, wheezing, rales, rhonchi, pharyngitis, nasal congestion, atelectasis |
| Vascular Disorders | peripheral ischemia, pallor, flushing |
1 Includes increased frequency of ventricular extrasystole and paired ventricular extrasystoles 2 Includes abdominal discomfort and stomach pain |
Administration site pain, skin discoloration, and itching have been reported in a healthy volunteer study.
Post-Market Adverse Drug Reactions
In addition, the following adverse events or adverse reactions have occurred under conditions where a causal association is uncertain or have been reported in the post-marketing experience. These reactions are listed by MedDRA System Organ Class (SOC), then by Preferred Term in order of severity.
Cardiac Disorders: cardiac arrest, ventricular fibrillation, myocardial infarction, cardiac failure congestive, hypertensive crisis, pulmonary edema, coronary arteriospasm, electromechanical dissociation, atrioventricular block, supraventricular extrasystoles, ventricular extrasystoles
General Disorders and Administration Site Conditions: injection site necrosis, infusion site vesicles, blistering
Metabolism and Nutrition Disorders: metabolic acidosis
Musculoskeletal and Connective Tissue Disorders: muscular weakness
Nervous System Disorders: neuropathy
Respiratory, Thoracic, and Mediastinal Disorders: respiratory failure
Renal and Urinary Disorders: renal tubular necrosis
Skin and Subcutaneous Tissue Disorders: skin exfoliation, angioedema, urticaria
DRUG INTERACTIONS
Overview
Because of BREVIBLOC products’ cardiac, pulmonary and/or other effects, there are many drugs and drug categories that can either enhance or inhibit its activity. For example, drugs and drug classes that enhance BREVIBLOC products’ effects result in the potential to lower blood pressure, reduce myocardial contractility, or interfere with sinus node function and electrical impulse propagation in the myocardium. In addition, drugs and drug categories that inhibit its effects may result in an increased dose requirement. Pharmacokinetic interactions of BREVIBLOC products with other drugs are also possible.
Drug-Drug Interactions
| Potential Drug-Drug Interactions | |||
|---|---|---|---|
| Name | Ref | Effect | Clinical Comment |
| Digoxin | CT | Concomitant administration of digoxin and BREVIBLOC products lead to an approximate 10-20% increase in digoxin blood levels at some time points. Digoxin did not affect BREVIBLOC products’ pharmacokinetics. | Although the interactions observed do not appear to be of major clinical importance, BREVIBLOC products should be titrated with caution in patients being treated concurrently with digoxin. |
| Morphine | CT | When the interaction of intravenous morphine and BREVIBLOC (esmolol hydrochloride) products were studied in normal subjects, no effect on morphine blood level was seen. However the steady-state blood levels of BREVIBLOC Injection / BREVIBLOC PREMIXED Injection were increased by 46% in the presence of morphine, but no other pharmacokinetic parameters were changed. | BREVIBLOC products should be titrated with caution in patients being treated concurrently with morphine. |
| Catecholamine-depleting drugs (e.g., reserpine) | T | Catecholamine-depleting drugs may have an additive effect when given with beta blocking agents. | Patients treated concurrently with BREVIBLOC products and a catecholamine depletor should therefore be closely observed for evidence of hypotension or marked bradycardia. |
| Succinylcholine | CT | The onset of neuromuscular blockade by succinylcholine was unaffected by BREVIBLOC Injection / BREVIBLOC PREMIXED Injection, but the duration of neuromuscular blockade was prolonged from five to eight minutes. | In certain clinical situations, the timely reversal of succinylcholine is important. As a result, in those situations, a prolongation of duration of the blockade from 5 to 8 minutes has clinical relevance. |
| Potential Drug-Drug Interactions |
|---|
| Name | Ref | Effect | Clinical Comment |
|---|---|---|---|
Calcium channel antagonists, in particular cardiodepressant calcium channel antagonists (e.g., verapamil, diltiazem) | L, CR | Fatal cardiac arrests have occurred in patients receiving BREVIBLOC products and intravenous verapamil. | Exercise caution when considering the use of BREVIBLOC products and calcium channel antagonists in patients with depressed myocardial function. (See CONTRAINDICATIONS) |
Sympathomimetic drugs (e.g. isoproterenol, terbutaline, epinephrine) | L | The effects of BREVIBLOC products may be counteracted by sympathomimetic drugs having beta-adrenergic agonist activity with concomitant administration. | The dose of either agent may need to be adjusted based on patient response, or use of alternate therapeutic agents considered. |
Substances that are vasoconstrictive and positive inotropic effects (e.g. epinephrine, norepinephrine, dopamine) | CT, CR | Risk of reducing cardiac contractility in the presence of high systemic vascular resistance. | BREVIBLOC products should not be used to control tachycardia in patients receiving drugs that are vasoconstrictive and have positive inotropic effects. (See WARNINGS AND PRECAUTIONS) |
| Tricyclic antidepressants (e.g., imipramine, amitriptyline) | T | As a class, these drugs antagonize peripheral alpha-1–adrenergic receptors, producing vasorelaxation and orthostatic hypotension. | Because of the potential pharmacodynamic interaction, BREVIBLOC products should be used with caution and only after careful individual assessment of the risks and expected benefits in patients receiving tricyclic antidepressants. |
| Inhalation anesthetics | L | All inhalational anesthetics exert a negative inotropic effect and beta blockers may potentiate the negative inotropic effect of inhalational anesthetics. | Because of the potential pharmacodynamic interaction, BREVIBLOC products should be used with caution and only after careful individual assessment of the risks and expected benefits in patients undergoing anesthesia with inhalation anesthetic agents. |
| Clonidine, Guanfacine, Moxonidine | L | Beta blockers increase the risk of clonidine-, guanfacine-, and moxonidine-withdrawal rebound hypertension. | If, during concomitant use of a beta blocker, antihypertensive therapy needs to be interrupted or discontinued, the beta blocker should always be the first medication discontinued, and the discontinuation should be gradual. |
| Potential Drug-Drug Interactions |
|---|
| Name | Ref | Effect | Clinical Comment |
|---|---|---|---|
| Antidiabetic agents | L | Concomitant use of insulin or other antidiabetic agents with beta blockers can increase the blood glucose–lowering effect of antidiabetic agents. | Beta blockers may mask tachycardia occurring with hypoglycemia, but other manifestations such as dizziness and sweating may not be masked. |
| Warfarin | L | Concomitant administration of BREVIBLOC products and warfarin does not alter warfarin plasma levels. BREVIBLOC product concentrations were equivocally higher when given with warfarin, but this is not likely to be clinically important. | Although this is not likely to be clinically important, as with all medications given in combination, patient should be observed for clinical effect. |
| Fingolimod | CT | Bradycardia | Concomitant use of fingolimod with beta blockers may potentiate bradycardic effects and is not recommended. Where such coadministration is considered necessary, appropriate monitoring at treatment initiation, i.e. at least overnight monitoring, is recommended. |
CT = Clinical Trial L = Literature T = Theoretical CR = Case Reports | |||
Drug-Food Interactions
Interactions with food have not been established.
Drug-Herb Interactions
Interactions with herbal products have not been established.
Drug-Laboratory Interactions
Interactions with laboratory tests have not been established.
DOSAGE AND ADMINISTRATION
Dosing Considerations
- BREVIBLOC products are for intravenous use only.
- BREVIBLOC products are for short-term use only (up to 24 hours).
- Dosage of BREVIBLOC products are individualized based on clinical response.
- Dosage needs to be titrated, using the ventricular rate and, if applicable, blood pressure as a guide.
- Patients with impaired renal function: BREVIBLOC products should be administered with caution to patients with impaired renal function. (See WARNINGS AND PRECAUTIONS)
Recommended Dose and Dosage Adjustment
Management of Perioperative Tachycardia and Hypertension:
Intubation: For the management of postintubation tachycardia and hypertension, give 1.5 mg/kg (up to a maximum of 100 mg) as a bolus injection (over 30 seconds) 1 to 2 minutes before intubation.
For Intra- and Postoperative Tachycardia and Hypertension:
For intraoperative and postoperative treatment of tachycardia and/or hypertension give 1.5 mg/kg (up to a maximum of 100 mg) as a bolus injection (over 30 seconds) followed by 0.15 mg/kg/min infusion. Adjust infusion rate as required up to 0.3 mg/kg/min to maintain desired heart rate and/or blood pressure.
Management of Atrial Fibrillation and Atrial Flutter:
Responses to BREVIBLOC Injection / BREVIBLOC PREMIXED Injection (esmolol hydrochloride) usually (over 95%) occur within the range of 0.05 to 0.2 mg/kg/min. The average effective dosage is approximately 0.1 mg/kg/min (7 mg/70 kg/min) although dosages as low as 0.025 mg/kg/min have been sufficient in some patients. Dosages as high as 0.3 mg/kg/min have been used but provided little added effect with an increased rate of adverse effects, and are not recommended. Dosage of BREVIBLOC (esmolol hydrochloride) products must be individualized by titration in which each step consists of a loading dose followed by a maintenance infusion.
To initiate treatment, administer a loading dose infusion of 0.5 mg/kg/min of BREVIBLOC Injection / BREVIBLOC PREMIXED Injection for one minute followed by a four-minute maintenance infusion of 0.05 mg/kg/min. If the therapeutic response is inadequate at this point, repeat the same loading dose and increase the maintenance infusion to 0.1 mg/kg/min.
Continue the titration procedure as above, repeating the loading dose (0.5 mg/kg/min for one minute), and increasing the maintenance infusion by increments of 0.05 mg/kg/min (for four minutes), up to a maximum infusion rate of 0.2 mg/kg/min. As the desired heart rate or a safety end point (e.g., lowered blood pressure) is approached, omit the loading dose and reduce the incremental dose of the maintenance infusion from 0.05 mg/kg/min to 0.025 mg/kg/min or lower. Alternatively, if desired, increase the interval between titration steps from five to ten minutes.
Maintenance dosages above 0.2 mg/kg/min have not been shown to have significantly increased benefits. The effectiveness of dosages above 0.3 mg/kg/min has not been studied.
| INDICATION | DOSING AND DOSE ADJUSTMENT |
|---|---|
| Perioperative Tachycardia and Hypertension | One to two minutes before intubation: Give a bolus injection (over 30 seconds) of 1.5 mg/kg (up to 100 mg) |
| Intra- and Postoperative Tachycardia and Hypertension | Give a bolus injection (over 30 seconds) of 1.5 mg/kg (up to 100 mg) Follow this with an infusion at a rate of 0.15 mg/kg/min Adjust infusion rate (up to 0.3 mg/kg/min) to maintain heart rate/blood pressure |
| Atrial Fibrillation and Atrial Flutter | Give a loading dose infusion at a rate of 0.5 mg/kg/min for 1 minute Follow with a maintenance infusion of 0.05 mg/kg/min for 4 minutes If the therapeutic response is inadequate Repeat the loading dose infusion of 0.5 mg/kg/min for 1 minute Increase maintenance infusion to 0.1 mg/kg/min for 4 minutes Continue procedure, repeating loading dose and Increasing maintenance infusion by increments of 0.05 mg/kg/min Once desired heart rate or safety endpoint is approached Omit loading dose and Reduce the incremental dose of the maintenance infusion from 0.05 mg/kg/min to 0.025 mg/kg/min or lower Alternatively, titration interval can be increased from 5 to 10 minutes. |
If a safety end point is exceeded, discontinue the infusion of BREVIBLOC (esmolol hydrochloride) products and re-start at a lower dose. In the event of an adverse reaction, the dosage infusion of BREVIBLOC (esmolol hydrochloride) products should be discontinued. If a reaction occurs at the site of the local infusion, an alternate infusion site should be used. Avoid the use of butterfly needles. The use of BREVIBLOC (esmolol hydrochloride) infusions up to 24 hours has been well documented.
BREVIBLOC Injection / BREVIBLOC PREMIXED Injection (esmolol hydrochloride) 10 mg/mL (100 mg/10 mL vial and 2500 mg/250 mL premixed bag) do not require dilution.
Directions for use
Parenteral drug products should be inspected visually for particulate matter and discoloration prior to administration, whenever solution and container permit. Samples containing visible particles should be discarded.
BREVIBLOC Injection 10 mg/mL (100 mg/10 mL Vials):
This dosage form is prediluted to 10 mL to provide a ready-to-use, iso-osmotic solution of 10 mg/mL esmolol hydrochloride in sodium chloride recommended for BREVIBLOC products intravenous administration. It may be used to administer the appropriate BREVIBLOC (esmolol hydrochloride) products loading dosage infusions by hand-held syringe while the maintenance infusion is being prepared.
BREVIBLOC PREMIXED Injection 10 mg/mL (2500 mg/250 mL Bags):
This dosage form is prediluted to 250 mL to provide a ready-to-use, iso-osmotic solution of 10 mg/mL esmolol hydrochloride in sodium chloride. BREVIBLOC PREMIXED Injection (10 mg/mL) is provided in ready-to-use bags with two ports, a medication port and a delivery port. The medication port is to be used solely for withdrawing an initial bolus from the bag; the medication withdrawal port is not intended for repeat bolus administration. The sterility of the premixed bag cannot be assured after repeat withdrawals from the bag. The use of aseptic technique is required when withdrawing the bolus dose. Do not add any additional medications to BREVIBLOC PREMIXED Injection. Each bag is for single-patient use only and contains no preservative. It is advised that once drug has been withdrawn from BREVIBLOC PREMIXED Injection, the bag should be used within 24 hours, with any unused portion discarded.
The BREVIBLOC PREMIXED Injection contains esmolol hydrochloride at a concentration of 10 mg/mL. The initial loading dose can be removed from the medication port of the premixed bag.
Missed Dose
This section is not applicable as BREVIBLOC Injection / BREVIBLOC PREMIXED Injection is an IV drug titrated by a physician.
Administration
CAUTION:
When using BREVIBLOC PREMIXED Injection (10 mg/mL), do not use plastic containers in series connections. Such use could result in an embolism due to residual air being drawn from the primary container before administration of the fluid from the secondary container is completed.
Do not introduce additives to BREVIBLOC Injection / BREVIBLOC PREMIXED Injection.
TO OPEN BREVIBLOC PREMIXED BAG:
Do not remove unit from overwrap until ready to use. Do not use if overwrap has been previously opened or damaged. The overwrap is a moisture barrier. The inner bag maintains sterility of the solution.
Tear overwrap at notch and remove premixed bag. Some opacity of the plastic due to moisture absorption during the sterilization process may be observed. This is normal and does not affect the solution quality or safety. The opacity will diminish gradually.
Check for minute leaks by squeezing inner bag firmly. If leaks are found, discard solution as sterility may be impaired.
Do not use unless the solution is clear, colourless to light yellow, and the plastic protector on the delivery port is intact. Do not use if the solution is cloudy or a precipitate is present.
Preparation for Intravenous Administration:
(use aseptic technique)
- 1. Suspend premixed bag from eyelet support.
- 2. Remove plastic protector from delivery port at bottom of bag.
- 3. Attach administration set. Refer to complete directions accompanying set.
OVERDOSAGE
| For management of a suspected drug overdose, contact your regional Poison Control Centre. |
Beta blocker overdose may be associated with cardiac and central nervous system effects, bronchospasm, vasospasm, hyperkalemia, and hypoglycemia. These effects may precipitate severe signs, symptoms, sequelae, and complications (for example, severe cardiac and respiratory failure, including shock and coma), and may be fatal.
Cardiac effects include bradycardia†, atrioventricular block (1st-, 2nd-, 3rd degree)†, junctional rhythms, intraventricular conduction delays, decreased cardiac contractility, hypotension†, cardiac failure (including cardiogenic shock)*, cardiac arrest/asystole†, and pulseless electrical activity†.
Central nervous system effects include respiratory depression, seizures, sleep and mood disturbances, fatigue, lethargy, and coma.
In addition, bronchospasm, mesenteric ischemia, peripheral cyanosis, hyperkalemia, and (especially in children) hypoglycemia may occur.
*has been reported with BREVIBLOC products
†has been reported as a fatal event with BREVIBLOC products
Cases of massive accidental overdoses of BREVIBLOC (esmolol hydrochloride) products have occurred due to dilution errors. Some of these overdoses have been fatal while others resulted in permanent disability. Bolus doses in the range of 625 mg to 3500 mg (12.5 - 70 mg/kg) have been fatal. Patients have recovered completely from overdoses as high as 1750 mg given over one minute or doses of 7500 mg given over one hour for cardiovascular surgery. The patients who survived appear to be those whose cardiovascular circulation could be supported until the effects of BREVIBLOC Injection / BREVIBLOC PREMIXED Injection resolved.
Continuous monitoring of the patient is required. The first step in the management of toxicity should be to discontinue the BREVIBLOC (esmolol hydrochloride) infusion. Then, because of its approximately 9-minute elimination half-life and based on the observed clinical effects, the following measures should also be considered:
- 1. General: BREVIBLOC Injection / BREVIBLOC PREMIXED Injection (esmolol hydrochloride) is a competitive antagonist of isoproterenol and hence larger doses of isoproterenol may be needed to reverse many of the effects of excessive dosage of BREVIBLOC products. However, the complications of excessive isoproterenol should not be overlooked.
- 2. Bradycardia: Intravenous administration of atropine or another anticholinergic drug. A heart rate increasing catecholamine may be indicated, and/or cardiac pacing may be necessary.
- 3. Heart block (second or third degree): Isoproterenol or transvenous cardiac pacemaker.
- 4. Congestive heart failure: Conventional therapy such as intravenous administration of a diuretic and/or digitalis glycoside. In shock due to inadequate cardiac contractility: intravenous administration of, for example, dopamine, dobutamine, isoproterenol. Glucagon has been reported to be useful.
- 5. Hypotension (depending on associated factors): Intravenous administration of fluids and/or vasopressor agents such as dopamine or norepinephrine.
- 6. Bronchospasm: Aminophylline or isoproterenol or other beta-2 agonists.
- 7. Hypoglycaemia: Intravenous glucose.
ACTION AND CLINICAL PHARMACOLOGY
Mechanism of Action
BREVIBLOC Injection / BREVIBLOC PREMIXED Injection (esmolol hydrochloride) is a beta-adrenergic receptor blocking agent with predominant blocking effect on beta-1 receptors. It does not possess significant intrinsic sympathomimetic or membrane stabilizing activity. BREVIBLOC Injection / BREVIBLOC PREMIXED Injection, which is administered only intravenously, has a rapid onset and a short duration of action.
Pharmacodynamics
In human electrophysiology studies, BREVIBLOC (esmolol hydrochloride) products produced effects typical of a beta-blocker: a decrease in the heart rate, increase in sinus cycle length, prolongation of the sinus node recovery time, prolongation of the AH interval during normal sinus rhythm and during atrial pacing, and an increase in antegrade Wenckebach cycle length.
Studies in normal volunteers have confirmed the beta-blocking activity of BREVIBLOC (esmolol hydrochloride) products, showing reduction in heart rate at rest and during exercise, and attenuation of isoproterenol-induced increases in heart rate. Blood levels of BREVIBLOC (esmolol hydrochloride) products have been shown to correlate with extent of beta-blockade.
Bolus injections of 50 and 100 mg BREVIBLOC (esmolol hydrochloride) Injection, given intraoperatively during general anesthesia, decreased heart rate by more than 20% within two minutes. Systolic blood pressure fell by 17% within five minutes. The effects lasted for up to ten minutes.
When given 1.5 to 2 minutes before intubation, 100 and 200 mg bolus injections of BREVIBLOC (esmolol hydrochloride) Injection attenuated the heart rate and blood pressure response to endotracheal intubation. No effects were detectable five minutes after the administration of BREVIBLOC Injection.
The haemodynamics were studied during continuous intravenous infusions in patients with elevated heart rate and acute ischemic heart disease (e.g., unstable angina pectoris or acute myocardial infarction). Titrated infusions of BREVIBLOC (esmolol hydrochloride) Injection, from 0.05 to 0.3 mg/kg/min, lowered heart rate and blood pressure. There were small increases in the left ventricular end diastolic pressure and pulmonary capillary wedge pressure, but were not considered to be clinically significant. Cardiac index, however, decreased. Cardiac index returned to pretreatment levels within 30 minutes after discontinuation of the infusion.
The relative cardioselectivity of BREVIBLOC Injection was demonstrated in mildly asthmatic patients. BREVIBLOC (esmolol hydrochloride) infusions (0.1, 0.2 and 0.3 mg/kg/min) produced no significant increases in specific airway resistance when compared to placebo. At 0.3 mg/kg/min, BREVIBLOC (esmolol hydrochloride) Injection produced slightly enhanced bronchomotor sensitivity to dry-air stimulus but was not considered clinically significant.
Pharmacokinetics
Absorption: Following bolus injections of BREVIBLOC (esmolol hydrochloride) products to healthy volunteers, the distribution and elimination half-lives averaged 1.4 and 10.9 minutes respectively. The blood concentrations of BREVIBLOC (esmolol hydrochloride) products were below quantifiable limits within 10 minutes.
Distribution: Following a loading infusion of 0.5 mg/kg/min over one minute, BREVIBLOC (esmolol hydrochloride) infusions of 0.050 to 0.3 mg/kg/min reach steady-state blood levels within five minutes with corresponding blood levels from 1.56 x 10⁻⁴ to 9.93 x 10⁻⁴ mg/mL. Steady-state blood levels increase linearly with dose over the dose range of 0.05 - 0.3 mg/kg/min. If a loading dose is not used, approximately 30 minutes are required to reach steady-state blood levels. Fifty-five percent of the amount in blood is bound to plasma proteins while the acid metabolite is only 10% bound. After cessation of the infusion, the blood levels of BREVIBLOC (esmolol hydrochloride) products decrease rapidly with an elimination half-life of nine minutes.
Metabolism: The total body clearance of BREVIBLOC (esmolol hydrochloride) products is about 20 L/hr/kg. Since this is greater than cardiac output, the metabolism of BREVIBLOC (esmolol hydrochloride) products is not limited by the rate of blood flow to metabolizing tissues such as the liver. The central and total volume of distribution were found to be 1.9 L/kg and 3.3 L/kg, respectively.
Excretion: Esterases in the red blood cell cytosol hydrolyse the ester link of BREVIBLOC (esmolol hydrochloride) products resulting in the formation of the corresponding free acid and methanol. This acid metabolite, which shows approximately 1/1500th the beta-blocking activity of esmolol in animal studies, has an elimination half-life of about 3.7 hours and is excreted in the urine with a clearance approximately equivalent to the glomerular filtration rate. Excretion of the acid metabolite is significantly decreased in patients with renal disease, with elimination half-life increased to about ten-fold that of patients with normal renal function, and plasma level was considerably elevated.
After several hours of infusion, at rates up to 0.3 mg/kg/min, methanol blood levels approximated endogenous levels (<10 μg/mL) and were less than 2% of levels usually associated with methanol toxicity.
Less than two percent of BREVIBLOC (esmolol hydrochloride) products is excreted unchanged in urine. After 24 hours, approximately 73 - 88% of the dose is recovered in the urine as the acid metabolite.
Special Populations and Conditions
Pediatrics: The safety and effectiveness of BREVIBLOC (esmolol hydrochloride) products in children have not been established.
Geriatrics: The safety and effectiveness of BREVIBLOC (esmolol hydrochloride) products in elders have not been established.
Gender: No data is available.
Race: No data is available.
Hepatic Insufficiency: The pharmacokinetics of BREVIBLOC Injection / BREVIBLOC PREMIXED Injection and of its major metabolite are unaltered in patients with hepatic cirrhosis.
Renal Insufficiency: In patients with end-stage renal disease, on haemo- or peritoneal dialysis, the pharmacokinetics of BREVIBLOC (esmolol hydrochloride) products were unchanged except for an increase in the volume of distribution in patients on peritoneal dialysis. The elimination half-life of the acid metabolite is increased about ten times in patients with renal disease.
Genetic Polymorphism: No data is available.
STORAGE AND STABILITY
Vial: Store at 15˚C to 25˚C.
Premixed Bag: Store at 15˚C to 25˚C. Protect from freezing. Avoid excessive heat.
BREVIBLOC (esmolol hydrochloride) products are not compatible with:
- sodium bicarbonate (5 %) solution (limited stability)
- furosemide (precipitation)
DOSAGE FORMS, COMPOSITION AND PACKAGING
BREVIBLOC Injection / BREVIBLOC PREMIXED Injection is provided in two different presentations, BREVIBLOC Injection in 10 mL vial and BREVIBLOC PREMIXED Injection in 250 mL bag. It is a clear, colourless to light yellow, sterile, nonpyrogenic, iso-osmotic solution of esmolol hydrochloride in sodium chloride.
Composition:
VIALS PREMIXED BAGS
Dosage form: Solution Solution
Concentration: 10 mg/mL 10 mg/mL
Volume: 10 mL 250 mL
________________________________________________________________
Esmolol Hydrochloride 10 mg/mL
Sodium Acetate Trihydrate, USP 2.8 mg/mL
Sodium Chloride, USP 5.9 mg/mL
Glacial Acetic Acid, USP 0.546 mg/mL
Sodium Hydroxide, as needed to adjust pH to: 4.5 – 5.5
Hydrochloric Acid, NF, as needed to adjust pH to: 4.5 – 5.5
Water for injection, USP q.s.
___________________________________________________________________
The calculated osmolarity of BREVIBLOC Injection / BREVIBLOC PREMIXED Injection is 312 mOsmol/L.
Packaging:
BREVIBLOC Injection (10 mg/mL) 10 mL Single Dose Vial:
BREVIBLOC Injection (esmolol hydrochloride) for direct intravenous injection is supplied in 10 mL amber glass vials at a concentration of 10 mg/mL, in boxes of 25 vials.
BREVIBLOC PREMIXED Injection (10 mg/mL) 250 mL Premixed Bag:
BREVIBLOC PREMIXED Injection (esmolol hydrochloride) for direct intravenous injection is supplied in 250 mL non-latex, non-PVC INTRAVIA bag with two PVC ports. The INTRAVIA bag is manufactured from a specially designed multilayer plastic (PL 2408). Solutions in contact with the plastic container leach out certain chemical compounds from the plastic in very small amounts; however, biological testing was supportive of the safety of the plastic container materials. BREVIBLOC PREMIXED Injection is supplied in boxes of 10 bags.
PART II: SCIENTIFIC INFORMATION
PHARMACEUTICAL INFORMATION
Drug Substance
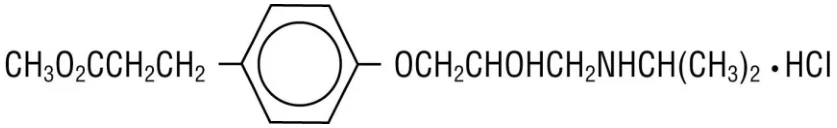
Proper name: Esmolol hydrochloride
Chemical name: (±)-Methyl p-[2-hydroxy-3-(isopropylamino) propoxy]
hydrocinnamate hydrochloride
Molecular formula and molecular mass: C16 H26 NO4 Cl, 331.8
Structural formula:
Physicochemical properties:
White to off-white powder
Solubility: Water: greater than 100 mg/mL; Alcohol: freely soluble pKa: 9.5
pH: 4.5 - 5.5 (10 mg/mL)
Partition Coefficient: octanol/water at pH 7.0 is 0.42 compared to 17 for propranolol
DETAILED PHARMACOLOGY
Animal data
BREVIBLOC Injection / BREVIBLOC PREMIXED Injection (esmolol hydrochloride) has a very short duration of pharmacological action in vivo because of its rapid metabolic inactivation. In animal studies it has been shown that this rapid inactivation occurs by hydrolysis of the methyl ester functionality in BREVIBLOC (esmolol hydrochloride) products to the corresponding carboxylic acid (ASL-8123) via blood and tissue esterases. The drug must be administered by the intravenous route and continuous infusion is required to achieve a prolonged pharmacological response. The following studies defined the pharmacokinetics of BREVIBLOC Injection / BREVIBLOC PREMIXED Injection and ASL-8123 in humans and provided the basis for the dosage regimen developed.
Human Studies
Please refer to Part I: HEALTH PROFESSIONAL INFORMATION – ACTION AND CLINICAL PHARMACOLOGY section.
TOXICOLOGY
Acute Toxicity:
| SPECIES | SEX | ROUTE | LD50 (mg/kg) | 95% C.I. (mg/kg) |
| Mouse | M/F | I.V.* | 92.9 | 86.6 - 100.2 |
| Rat | M/F | I.V.* | 70.9 | 59.0 - 82.0 |
| Rabbit | M/F | I.V.* approx. | 40 | - |
| Dog (Beagle) | M/F | I.V.* | 31.6 | 26.3 - 38.0 |
| Rat | M/F | I.V.** | 66.7 | 62.8 - 70.8 |
| Rat | M/F | Oral | 8.9 g/kg | 8.3 - 9.6 g/kg |
* Esmolol in saline
** 10% esmolol in formulation containing propylene glycol, alcohol and sodium acetate buffer.
After intravenous administration, all deaths occurred within approximately 10 minutes of dosing. Pharmacotoxic signs included dyspnea, prostration, convulsions, vocalizations (dogs), papillary constriction (rabbits), progressing to papillary dilation (rabbits and dogs) and less frequently, hyperpnea, hypokinesia, tremors, and sedation. All signs were absent within one hour after dosing and no delayed toxicity was observed during the two-week observation period. After oral administration, similar pharmacotoxic signs were observed, but deaths occurred for up to two days after dosing.
Long-Term Toxicity:
| SPECIES/ STRAIN | SEX M F | DOSAGE | ROUTE | DURATION OF DOSING | TOXICITY SIGNS |
|---|---|---|---|---|---|
| Rat (CD) | 30 30 | 0, 12, 18, 27, 40, 60 mg/kg | Single IV dose/day | 7 Days | 12, 18, 27 mg/kg: reduced activity, sedation, respiratory depression, hyperactivity: 40, 60 mg/kg: dyspnea, prostration convulsions, tremors, ataxia, hyperpnea, unconsciousness. Deaths (all within 5 min. of dosing): 3 (60 mg/kg), 2 (40 mg/kg). |
| Rat (CD) | 60 60 | 0 (Vehicle), 5, 20, 40 mg/kg | Single IV dose/day | 14 Days | 20 and 40 mg/kg: reduced motor activity, ataxia, respiratory distress (½ to 5 min. post-dose). 40 mg/kg: involuntary twitching pale eyes, pale skin, prostration. Deaths: 1 (control) 5 (40 mg/kg). |
| Dog (Beagle) | 6 6 | 0, 50, 100, 200, 500, 1000 μg/kg/min | Continuous IV Infusion | 5 Days | 100 μg/kg/min: sedation and diarrhea. 500 μg/kg/min: head tremors and muscle rigidity. 1000 μg/kg/min: ataxia, head tremors, muscle rigidity, salivation, emesis, unsteady gait, disorientation, convulsions, prostration, vocalization, ptosis. No deaths during dosing. Slight decrease in body weight in all groups including controls. Gross pathology: haemorrhagic spots on kidneys of 4 treated dogs. No drug-related histopathological changes. |
| Dog (Beagle) | 6 6 | 0 (Saline), 400, 800 μg/kg/min | Continuous IV Infusion | 7 Days | 800 μg/kg/min: head tremors. Deaths: 1 (800 μg/kg/min) on Day 7 due to overdose of anesthesia. |
| Dog (Beagle) | 12 12 | 0 (Vehicle), 100, 400, 800, μg/kg/min (Infusion solution = 10 mg/mL) | Continuous IV Infusion (10 mg/mL) | 14 Days | 800 μg/kg/min: sporadic decreased activity or emesis in 4 dogs. One male exhibited prostration, salivation, non-response to stimuli, disorientation, ataxia and decreased muscle tone. Only high-dose males had a significant loss of weight (5%). BUN slightly elevated in high-dose females. No drug-related macroscopic/microscopic changes, organ weights differences observed (except for liver weights in high-dose males). |
The acid metabolite of esmolol administered intravenously in mice as a bolus in normal saline had an LD50 of 452 mg/kg (95% C.I.: 417 - 488 mg/kg). Pharmacotoxic signs were similar to those of esmolol.
Teratology and Reproduction Studies
Intravenous administration of esmolol at dosages between 1.0 and 3.0 mg/kg/min in rats and 0.5 to 1.0 mg/kg/min in rabbits for 30 minutes daily during organogenesis produced no detectable maternotoxic, embryotoxic or teratogenic effects. Administration of esmolol at 10 mg/kg/min to rats and 2.5 mg/kg/min to rabbits produced maternotoxicity and embryotoxicity. No teratogenic effects were observed, however, at these high dosages.
Vascular Irritation Studies
Venous irritation of esmolol formulation was studied by infusing the drug into the jugular vein of dogs for up to 72 hours. Formulations containing 10 mg/mL of esmolol were generally well tolerated for up to 24 hours, at infusion rates of 0.5 mg/kg/min without serious irritation. Thrombophlebitis, erythema and inflammation occurred during longer infusions as with undiluted drug formulation. Drug vehicle or diluent contributed little to the irritation observed.
REFERENCES
- 1. Abrams J, Allen J, Allin D, Anderson J, Anderson S, Blanski L, Chadda K, Dibianco R, Favrot L, Gonzalez J, Horowitz L, Laddu AR, Lee R, MacCosbe P, Morganroth J, Narula O, Singh B, Singh J, Steck J, Swerdlow C, Turlapaty P, Waldo A. Efficacy and Safety of Esmolol vs Propranolol in the Treatment of Superventricular Tachyarrhythmias - a Multicenter Double-Blind Clinical Trial. Amer Heart J 1985; 110:913-922.
- 2. Achari R, Drissel D, Matier WL, Hulse JD. Metabolism and Urinary Excretion of Esmolol in Humans. J Clin Pharmacol 1986; 26:44-47.
- 3. Anderson S, Blankski L, Byrd RC, Das G, Engler R, Laddu A, Lee R, Rajfer S, Schroeder J, Steck J, Sung R, Turlapaty P, Williams D, Wilner G, Zoble R. Comparison of the Efficacy and Safety of Esmolol, a Short_Acting Beta-Blocker, with Placebo in the Treatment of Superventricular Tachyarrhythmias. Amer Heart J 1986; 111:42-48.
- 4. Byrd R, Sung RJ, Marks J, Parmley WW. Safety and Efficacy of Esmolol (ASL-8052: an Ultrashort-Acting Beta-Adrenergic Blocking Agent) for Control of Ventricular Rate in Supraventricular Tachycardias. J Amer Coll Cardiol 1984; 3:394-399.
- 5. Gold, MI Brown M, Coverman S, Herrington C. Heart Rate and Blood Pressure Effects of Esmolol After Ketamine Induction and Intubation. Anesthesiology 1986;64:718-723.
- 6. Gray RJ, Bateman TM, Czer LSC, Conklin CM, Matloff JM. Esmolol - A New Ultrashort Acting Beta-Blocking Agent for Rapid Control of Heart Rate in Postoperative Supraventricular Tachyarrhymias. J Amer Coll Cardiol 1985; 5:1451-56.
- 7. Gray RJ, Bateman TM, Czer LSC, Conklin C, Matloff JM. Use of Esmolol in Hypertension After Cardiac Surgery. Amer J Cardiol 1985; 56:49F-56F.
- 8. Greenspan AM, Scott R, Spielman SR, Horowitz LN, Senior S, Steck J, Laddu A. Electrophysiology of Esmolol. Amer J Cardiol 1985; 56:19F-26F.
- 9. Iskandrian AS, Hakki AH, Laddu AR. Effects of Esmolol on Cardiac Function: Evaluation by Noninvasive Techniques. Amer J Cardiol 1985; 56:27F-32F.
- 10. Kloner RA, Kirshenbaum J, Lange R, Antman EM, Braunwald E. Experimental and Clinical Observations on the Efficacy of Esmolol in Myocardial Ischemia. Amer J Cardiol 1985; 56:40F-48F.
- 11. Menkhaus PG, Reves JG, Kissin I, Alvis JM, Govier AV, Samuelson PN, Lell WA, Henling CE, Bradley E. Cardiovascular Effects of Esmolol in Anesthetized Humans. Anesth Anal 1985; 64:327-334.
- 12. Murthy VS, Hwang TF, Sandage BW, Laddu AR. Esmolol and the Adrenergic Response to Perioperative Stimuli. J Clin Pharmacol 1986; 26(Suppl A):A27-A35.
- 13. Murthy VS, Patel KD, Elangovan RG, Hwang TF, Solocheck SM, Steck JD, Laddu AR. Cardiovascular and Neuromuscular Effects of Esmolol During Induction of Anesthesia. J Clin Pharmacol 1986; 26:351-57.
- 14. Reves JG, and Flezzani P. Perioperative Use of Esmolol. Amer J Cardiol 1985; 56-57F-62F.
- 15. Sinetos AL, Hulse J, Pritchett ELC. Pharmacokinetics and Pharmacodynamics of Esmolol Administered as an Intravenous Bolus. Clin Pharmacol Ther 1987; 41:112-7.