


Product Monograph - Cisplatin Injection (Fresenius Kabi Canada)
RECENT MAJOR LABEL CHANGES
| 1 INDICATIONS, 1.1 Pediatrics | 04/2024 |
|---|---|
| 1 INDICATIONS, 1.2 Geriatrics | 04/2024 |
| 3 SERIOUS WARNINGS AND PRECAUTIONS BOX | 04/2024 |
| 4 DOSAGE AND ADMINISTRATION, 4.4 Administration | 04/2024 |
| 7 WARNINGS AND PRECAUTIONS, Carcinogenesis and Mutagenesis | 04/2024 |
| 7 WARNINGS AND PRECAUTIONS, Ear/Nose/Throat | 04/2024 |
| 7 WARNINGS AND PRECAUTIONS, Gastrointestinal | 04/2024 |
| 7 WARNINGS AND PRECAUTIONS, Hematologic | 04/2024 |
| 7 WARNINGS AND PRECAUTIONS, Immune | 04/2024 |
| 7 WARNINGS AND PRECAUTIONS, Injection Site Reactions | 04/2024 |
| 7 WARNINGS AND PRECAUTIONS, Monitoring and Laboratory Tests | 04/2024 |
| 7 WARNINGS AND PRECAUTIONS, Musculoskeletal and connective tissue disorders | 04/2024 |
| 7 WARNINGS AND PRECAUTIONS, Neurologic | 04/2024 |
| 7 WARNINGS AND PRECAUTIONS, Renal | 04/2024 |
| 7 WARNINGS AND PRECAUTIONS, Fertility | 04/2024 |
| 7 WARNINGS AND PRECAUTIONS, 7.1 2 Breast-feeding | 04/2024 |
| 7 WARNINGS AND PRECAUTIONS, 7.1.4 Geriatrics | 04/2024 |
TABLE OF CONTENTS
Sections or subsections that are not applicable at the time of authorization are not listed.
RECENT MAJOR LABEL CHANGES ............................................................................................. 2
TABLE OF CONTENTS ............................................................................................................... 2
PART I: HEALTH PROFESSIONAL INFORMATION ....................................................................... 5
1 INDICATIONS ................................................................................................................ 5
1.1 Pediatrics ................................................................................................................. 5
1.2 Geriatrics ................................................................................................................. 5
2 CONTRAINDICATIONS .................................................................................................. 5
3 SERIOUS WARNINGS AND PRECAUTIONS BOX ............................................................. 6
4 DOSAGE AND ADMINISTRATION .................................................................................. 6
4.2 Recommended Dose and Dosage Adjustment ......................................................... 6
4.3 Reconstitution ......................................................................................................... 7
4.4 Administration ......................................................................................................... 7
5 OVERDOSAGE ............................................................................................................... 7
6 DOSAGE FORMS, STRENGTHS, COMPOSITION AND PACKAGING .................................. 8
7 WARNINGS AND PRECAUTIONS ................................................................................... 8
7.1 Special Populations ................................................................................................ 14
7.1.1 Pregnant Women .............................................................................................. 14
7.1.2 Breast-feeding ................................................................................................... 14
7.1.3 Pediatrics........................................................................................................... 14
7.1.4 Geriatrics ........................................................................................................... 14
8 ADVERSE REACTIONS ................................................................................................. 14
9 DRUG INTERACTIONS ................................................................................................. 18
9.2 Drug Interactions Overview ................................................................................... 18
9.4 Drug-Drug Interactions .......................................................................................... 18
9.5 Drug-Food Interactions .......................................................................................... 19
9.6 Drug-Herb Interactions .......................................................................................... 19
9.7 Drug-Laboratory Test Interactions ......................................................................... 19
10 CLINICAL PHARMACOLOGY ........................................................................................ 19
10.1 Mechanism of Action ............................................................................................. 19
10.2 Pharmacodynamics ................................................................................................ 20
10.3 Pharmacokinetics ................................................................................................... 20
11 STORAGE, STABILITY AND DISPOSAL .......................................................................... 21
12 SPECIAL HANDLING INSTRUCTIONS ............................................................................ 21
PART II: SCIENTIFIC INFORMATION ........................................................................................ 22
13 PHARMACEUTICAL INFORMATION ............................................................................. 22
14 CLINICAL TRIALS ......................................................................................................... 22
15 MICROBIOLOGY ......................................................................................................... 22
16 NON-CLINICAL TOXICOLOGY ...................................................................................... 23
17 SUPPORTING PRODUCT MONOGRAPHS ..................................................................... 24
PATIENT MEDICATION INFORMATION ................................................................................... 25
PART I: HEALTH PROFESSIONAL INFORMATION
1 INDICATIONS
Cisplatin Injection is indicated as palliative therapy, to be employed in addition to other modalities, or in established combination therapy with other chemotherapeutic agents in the following:
- Metastatic Testicular Tumors: In patients who have already received appropriate surgical and/or radiotherapeutic and/or chemotherapeutic procedures.
- Metastatic Ovarian Tumors: As secondary therapy in patients refractory to standard chemotherapy.
- Advanced Bladder Cancer: As a single agent for patients with transitional cell bladder cancer.
1.1 Pediatrics
Ototoxic effects may be more severe in children particularly in patients less than 5 years of age (see 7.1.3 Pediatrics).
1.2 Geriatrics
Geriatric patients, patients with baseline renal impairment, patients who are taking other nephrotoxic drugs, or patients who are not well hydrated may be more susceptible to nephrotoxicity. Geriatric patients may be more susceptible to myelosuppression. Geriatric patients may be more susceptible to peripheral neuropathy. See 7.1.4 Geriatric.
2 CONTRAINDICATIONS
- Cisplatin Injection is contraindicated in patients with pre-existing renal impairment and hearing impairment, unless in the judgement of the physician and patient, the possible benefits of treatment outweigh the risks.
- Cisplatin Injection should not be employed in myelosuppressed patients.
- Cisplatin Injection is contraindicated in individuals who have demonstrated a previous hypersensitivity to it or other platinum-containing compounds or to any ingredient in the formulation, including any non-medicinal ingredient, or component of the container (see 6 DOSAGE FORMS, STRENGTHS, COMPOSITION AND PACKAGING).
When used as indicated, the physician must carefully weigh the therapeutic benefit versus risk of toxicity which may occur.
3 SERIOUS WARNINGS AND PRECAUTIONS BOX
Serious Warnings and Precautions
CISPLATIN INJECTION IS A CYTOTOXIC DRUG THAT MUST BE ADMINISTERED ONLY BY PHYSICIANS EXPERIENCED WITH CANCER CHEMOTHERAPEUTIC DRUGS. BLOOD COUNTS AS WELL AS RENAL AND HEPATIC FUNCTION TESTS SHOULD BE TAKEN REGULARLY. DISCONTINUE THE DRUG IF ABNORMAL DEPRESSION OF BONE MARROW OR ABNORMAL RENAL OR HEPATIC FUNCTION IS SEEN.
|
|---|
4 DOSAGE AND ADMINISTRATION
4.2 Recommended Dose and Dosage Adjustment
The recommended dose of Cisplatin Injection in adults and children as single-agent therapy is 50 to 75 mg/m2 as a single intravenous dose every 3 to 4 weeks, or 15 to 20 mg/m2 intravenous daily for 5 days, every 3 to 4 weeks.
A repeat course of Cisplatin Injection should not be given until the serum creatinine is below 1.5 mg/100 mL and/or the BUN is below 25 mg/100 mL. A repeat course should not be given until circulating blood elements are at an acceptable level (platelets ≥100,000 cells/mm3, WBC ≥4,000 cells/mm3). Subsequent dose of Cisplatin Injection should not be given until an audiometric analysis indicates that auditory acuity is within normal limits.
When employed in combination with other antitumor drugs, the dose of Cisplatin Injection should be adjusted appropriately.
4.3 Reconstitution
Preparation of intravenous solutions:
Intravenous needles, syringes or sets having aluminum components should not be employed in preparation or administration of Cisplatin Injection solutions. An interaction will occur between aluminum and platinum from cisplatin, causing formation of a black precipitate, which is visible in the reconstituted solution, and a loss of potency.
Dilute the prepared Cisplatin Injection in 2 litres of 5% Dextrose in 0.45% Sodium Chloride Injection or 5% Dextrose in 0.3% Sodium Chloride Injection, containing 37.5 g of Sterile Mannitol.
Diluted Cisplatin Injection solution is suitable for intravenous infusion. This solution is not preserved and it should be used within 24 hours. Any unused portion should be discarded after that time, in order to avoid risk of microbial contamination.
As with all parenteral drug products, intravenous admixtures should be inspected visually for clarity, particulate matter, precipitate, discolouration and leakage prior to administration, whenever solution and container permit. Solutions showing haziness, particulate matter, precipitate, discolouration or leakage should not be used.
4.4 Administration
Pre-treatment hydration with 1 to 2 L of fluid infused for 8 to 12 hours prior to a cisplatin dose is recommended. The drug is then diluted in 2 liters of 5% dextrose in 1/2 or 1/3 normal saline containing 37.5 g of mannitol, and infused over a 6 to 8-hour period. Adequate hydration and urinary output must be maintained during the following 24 hours.
Cisplatin is a cytotoxic agent. Caution should be utilized during handling and preparation. Use of gloves and other protective clothing to prevent skin contact is recommended (see 4.3 Reconstitution and 7 WARNINGS AND PRECAUTIONS, General and 12 SPECIAL HANDLING INSTRUCTIONS). If cisplatin solution contacts the skin, immediately wash thoroughly with soap and water. If cisplatin solution contacts mucous membranes, flush thoroughly with water.
5 OVERDOSAGE
CAUTION SHOULD BE USED TO PREVENT INADVERTENT OVERDOSAGE WITH CISPLATIN INJECTION.
Acute overdosage with this drug may result in kidney failure, liver failure, deafness, ocular toxicity (including detachment of the retina), significant myelosuppression, intractable nausea and vomiting and/or neuritis. In addition, death can occur following overdosage.
No proven antidote has been established for cisplatin overdosage. Hemodialysis, even when initiated for hours after overdosage, appears to have little effect on removing platinum from the body because of rapid and high degree of protein binding of cisplatin. Management of overdosage should include general supportive measures to sustain the patient through the period of toxicity that may occur. Patients should be monitored for 3 – 4 weeks in case of delayed toxicity.
For management of a suspected drug overdose, contact your regional poison control centre.
6 DOSAGE FORMS, STRENGTHS, COMPOSITION AND PACKAGING
Table – Dosage Forms, Strengths, Composition and Packaging
| Route of Administration | Dosage Form/ Strength/Composition | Non-medicinal Ingredients |
|---|---|---|
| Intravenous infusion | Sterile solution 1 mg/mL cisplatin | Sodium chloride, Water for injection. Hydrochloric acid and Sodium hydroxide are added as a pH adjuster. |
Cisplatin Injection, 1 mg/mL is supplied as a sterile solution in single-use glass amber vials (single packs), containing 50 mg cisplatin in 50 mL, 100 mg cisplatin in 100 mL, and 200 mg cisplatin in 200 mL.
Vial stoppers do not contain natural rubber latex.
Cisplatin Injection is preservative-free.
7 WARNINGS AND PRECAUTIONS
See 3 WARNINGS AND PRECAUTIONS BOX
General
CISPLATIN INJECTION IS A CYTOTOXIC DRUG AND SHOULD BE USED ONLY BY PHYSICIANS EXPERIENCED WITH CANCER CHEMOTHERAPEUTIC DRUGS. BLOOD COUNTS AS WELL AS RENAL AND HEPATIC FUNCTION TESTS SHOULD BE TAKEN REGULARLY. DISCONTINUE THE DRUG IF ABNORMAL DEPRESSION OF BONE MARROW OR ABNORMAL RENAL OR HEPATIC FUNCTION IS SEEN.
Cisplatin Injection should be administered under the supervision of a qualified physician experienced with the use of antineoplastic therapy. The benefit to patient versus risk of toxicity must be carefully weighed. Appropriate management of therapy and complications is possible only when adequate diagnostic and treatment facilities are readily available.
An interaction will occur between aluminum and platinum from cisplatin, causing a black precipitate which is visible in the solution (see 4.3 Reconstitution, Preparation of intravenous solutions).
As with other potentially toxic compounds, caution should be exercised in handling the solution of cisplatin (see 4.3 Reconstitution, 4.4 Administration, 7 WARNINGS AND PRECAUTIONS, General, 12 SPECIAL HANDLING INSTRUCTIONS). Skin reactions associated with accidental exposure to cisplatin may occur. The use of gloves is recommended. If cisplatin solution contacts the skin, immediately wash thoroughly with soap and water. If cisplatin solution contacts mucous membranes, flush thoroughly with water.
Carcinogenesis and Mutagenesis
Cisplatin has been found to have carcinogenic potential in laboratory animals. There have been reports of acute myelogenous leukemias and myelodysplastic syndromes arising in patients who have been treated with cisplatin, mostly when given in combination with other potentially leukemogenic agents. The development of acute leukemia coincident with the use of cisplatin (secondary acute leukemia) has been reported in humans. In these reports cisplatin was generally given in combination with other leukemogenic agents (see 8 ADVERSE REACTIONS and 16 NON-CLINICAL TOXICOLOGY).
Cardiovascular
Cisplatin has been found to be associated with cardiovascular toxicity (see 3 SERIOUS WARNINGS AND PRECATIONS BOX and 8 ADVERSE REACTIONS). A significant increase in the risk of venous thromboembolic events has been reported in patients with advanced solid tumors and treated with cisplatin. Vascular toxicities have been reported. The events were clinically heterogeneous and included myocardial infarction, cerebrovascular accident (hemorrhagic and ischemic stroke), thrombotic microangiopathy (hemolytic uremic syndrome) or cerebral arteritis.
There are also reports of Raynaud’s phenomenon occurring in patients treated with the combination of bleomycin, vinblastine with or without cisplatin. It has been suggested that hypomagnesemia can occur with the use of cisplatin. However, it is currently unknown if the cause of Raynaud’s phenomenon in these cases is the disease, underlying vascular compromise, bleomycin, vinblastine, hypomagnesemia or a combination of any of these factors.
Cases of pulmonary embolism (including fatalities) have been reported (see 3 SERIOUS WARNINGS AND PRECAUTIONS BOX and 8 ADVERSE REACTIONS).
Ear/Nose/Throat
Cisplatin injection can cause ototoxicity, which is cumulative and may be severe. Ototoxicity has been observed in up to 31% of patients treated with a single dose of cisplatin, 50 mg/m2, and is manifested by tinnitus and/or hearing loss in the high frequency range (4000 to 8000 Hz). Decreased ability to hear normal conversational tones may occur occasionally. Hearing loss can be unilateral or bilateral and tends to become more frequent and severe with repeated doses; however, deafness after the initial dose of cisplatin has been reported rarely. It is unclear whether cisplatin-induced ototoxicity is reversible. Additional risk factors for ototoxicity include simultaneous cranial irradiation, treatment with other ototoxic drugs and renal impairment.
Ototoxic effects may be more severe in children particularly in patients less than 5 years of age. The prevalence of hearing loss in pediatric patients is estimated to be 40-60%. Careful monitoring of audiometry should be performed prior to initiation of therapy and prior to subsequent doses of cisplatin. Vestibular toxicity has also been reported. Consider audiometric and vestibular testing in all pediatric patients receiving cisplatin.
Concurrent and/or sequential administration of ototoxic drugs such as aminoglycoside antibiotics or loop diuretics may increase the potential of cisplatin to cause ototoxicity, especially in the presence of renal impairment (see 9.4 Drug-Drug Interactions.). Ifosfamide may increase hearing loss due to cisplatin.
Gastrointestinal
Cisplatin is a highly emetogenic antineoplastic agent. Premedicate with anti-emetic agents. Marked nausea and vomiting occurred in almost all patients treated with cisplatin occasionally severe causing discontinuation. Nausea and vomiting may begin within 1 to 4 hours after treatment and last up to 72 hours. Maximal intensity occurs 48 to 72 hours after administration. Various degrees of vomiting, nausea, and/or anorexia may persist for up to 1 week after treatment.
Delayed nausea and vomiting (beginning or persisting 24 hours or more after chemotherapy) have occurred in patients attaining complete emetic control on the day of cisplatin therapy. Consider the use of additional anti-emetics following infusion.
Diarrhea and stomatitis have also been reported (See 8 ADVERSE REACTIONS).
Hematologic
Myelosuppression occurs in 25 to 30% of patients treated with cisplatin. WBC and platelet nadirs generally occur after about 2 weeks with levels returning to pre-treatment values in most patients within 4 weeks. Cisplatin may cause anemia, which is occasionally caused by hemolysis. The nadirs in circulating platelets and leukocytes occur between days 18 and 23 (range 7.5 to 45), with most patients recovering by day 39 (range 13 to 62) (see 8 ADVERSE REACTIONS).
Leukopenia and thrombocytopenia are dose-related, and may become clinically relevant in patients receiving high doses of cisplatin or in patients who have received prior myelosuppressive treatments. Leukopenia and thrombocytopenia are more pronounced at higher doses (>50 mg/m2) (see 8 ADVERSE REACTIONS).
Anemia (decrease of 2 g hemoglobin/100 mL) occurs at approximately the same frequency and with the same timing as leukopenia and thrombocytopenia.
Neutropenia, including fatal cases, has also been reported.
Cisplatin has been shown to sensitize red blood cells, sometimes resulting in a direct Coombs’ positive hemolytic anemia. The incidence, severity and relative importance of this effect in relation to other hematologic toxicity has not been established, but the possibility of a hemolytic process should be considered in any person who is receiving cisplatin and has an unexplained fall in hemoglobin. The hemolytic process reverses on cessation of therapy.
Fever and infection have been reported in patients with neutropenia. Potential fatalities due to infection (secondary to myelosuppression) have been reported. Geriatric patients may be more susceptible to myelosuppression.
Perform standard hematologic tests before initiating Cisplatin Injection, before each subsequent course, and as clinically indicated. Closely monitor patients for the development of signs and symptoms of infection during and after treatment with Cisplatin Injection. For patients who develop severe myelosuppression during treatment with Cisplatin Injection, consider dose modifications and manage according to clinical treatment guidelines.
Hepatic
Transient elevation of hepatic enzymes and bilirubin can occur when cisplatin is administered in recommended doses.
Immune
Cisplatin injection can cause severe hypersensitivity reactions, including anaphylaxis and death. Manifestations have included facial edema, wheezing, tachycardia, and hypotension. Hypersensitivity reactions have occurred within minutes of administration to patients with prior exposure to cisplatin injection and have been alleviated by administration of epinephrine, corticosteroids and antihistamines.
Monitor patients receiving Cisplatin Injection for possible hypersensitivity reactions. Ensure supportive equipment and medications are available to treat severe hypersensitivity reactions. Severe hypersensitivity reactions require immediate discontinuation of Cisplatin Injection and aggressive therapy. Patients with a history of severe hypersensitivity reactions should not be rechallenged with cisplatin injection (see 2 CONTRAINDICATIONS). Cross-reactivity between platinum-based antineoplastic agents has been reported. Cases of severe hypersensitivity reactions have recurred after rechallenging patients with a different platinum agent.
Infections and infestations
Infection and sepsis (including fatalities) have been reported. Tuberculosis has been reported.
Injection Site Reactions
Injection site reactions can occur during the administration of cisplatin injection. Local soft tissue toxicity has been reported following extravasation of cisplatin injection. Severity of the local tissue toxicity appears to be related to the concentration of the cisplatin injection solution. Infusion of solutions with a cisplatin injection concentration greater than 0.5 mg/mL may result in tissue cellulitis, fibrosis, necrosis, pain, edema, and erythema.
Because of the possibility of extravasation, closely monitor the infusion site during drug administration.
Monitoring and Laboratory Tests
- Cisplatin produces cumulative nephrotoxicity which can be potentiated by aminoglycoside antibiotics. Serum creatinine, BUN, creatinine clearance, magnesium, sodium, potassium and calcium levels should be measured prior to initiating therapy and prior to each subsequent course.
- Ototoxicity of cisplatin is cumulative, audiometric testing should be performed prior to initiating therapy and prior to each subsequent dose of drug (see 8 ADVERSE REACTIONS).
- Peripheral blood counts should be monitored weekly. Therapy should be interrupted accordingly.
- Liver function should be monitored periodically.
- Neurologic examinations should also be performed regularly (see 8 ADVERSE REACTIONS).
Serum Electrolyte Disturbances:
Hypomagnesemia, hypocalcemia, hyponatremia, hypokalemia and hypophosphatemia have been reported to occur in patients treated with cisplatin and are probably related to renal tubular damage. Tetany has occasionally been reported in those patients with hypocalcemia and hypomagnesemia. Generally, normal serum electrolyte levels are restored by administering supplemental electrolytes and discontinuing cisplatin. Inappropriate antidiuretic hormone syndrome has also been reported.
Musculoskeletal and connective tissue disorders
Arthralgia/myalgia has been reported.
Neurologic
Cisplatin injection can cause dose-related peripheral neuropathy that becomes more severe with repeated courses of the drug. Neuropathy can also have a delayed onset from 3 to 8 weeks after the last dose of cisplatin injection. The neuropathy may progress further even after stopping treatment. These neuropathies may be irreversible and are seen as paresthesia in a stocking-glove distribution, areflexia, and loss of proprioception and vibratory sensation. Loss of motor function has also been reported. Serious events of leukoencephalopathy and posterior reversible encephalopathy syndrome including fatalities have been reported in post-market setting (see 3 SERIOUS WARNINGS AND PRECAUTIONS BOX and 8 ADVERSE REACTIONS).
Neurotoxicity, usually characterized by peripheral neuropathies, has occurred in some patients. Neuropathies resulting from cisplatin treatment may occur after prolonged therapy (4 to 7 months), however, neurologic symptoms have been reported to occur after a single dose. The neuropathy may progress after stopping the treatment. Lhermitte’s sign, dorsal column myelopathy, autonomic neuropathy, leukoencephalopathy and posterior reversible encephalopathy syndrome have also been reported.
Cisplatin therapy should be discontinued when symptoms are first observed. Preliminary evidence suggests peripheral neuropathy may be irreversible in some patients.
Perform a neurological examination before initiating Cisplatin Injection, at appropriate intervals during therapy, and after completion of therapy. Consider discontinuation of Cisplatin Injection for patients who develop symptomatic peripheral neuropathy. Geriatric patients may be more susceptible to peripheral neuropathy.
Muscle cramps of sudden onset and short duration have been reported. These were usually observed in patients who had received a relatively high cumulative dose of cisplatin, and who had a relatively advanced stage of peripheral neuropathy.
Loss of taste, seizures, slurred speech and memory loss have also been reported.
Ocular Toxicity
Optic neuritis, papilledema and cerebral blindness have been reported infrequently in patients receiving standard recommended doses of cisplatin. Improvement and/or total recovery usually occurs after discontinuing cisplatin. Steroids, with or without mannitol, have been used, however, efficacy has not been established.
Blurred vision and altered colour perception have been reported after the use of regimens with higher doses of cisplatin or greater dose frequencies than those recommended. The altered colour perception manifests as a loss of colour discrimination, particularly in the blue-yellow axis. The only finding on funduscopic exam is irregular retinal pigmentation of the macular area.
Other toxicities
Other toxicities reported to occur infrequently are cardiac abnormalities, hiccups, elevated serum amylase and rash. Alopecia has also been reported.
Local soft tissue toxicity has rarely been reported following extravasation of cisplatin. Infiltration of solutions of cisplatin may result in tissue cellulitis, fibrosis, necrosis, phlebitis, pain, edema and erythema. Pyrexia, asthenia, malaise have also been reported.
Renal
Ensure adequate hydration before, during, and after Cisplatin Injection administration (see 4.4 Administration). Cisplatin can cause severe renal toxicity, including acute renal failure.
At the recommended dosage, cisplatin should not be given more frequently than once every 3 to 4 weeks. Dose-related and cumulative renal insufficiency is the major dose-limiting toxicity of cisplatin. Renal toxicity has been noted in 28-36% of patients treated with a single dose of 50 mg/m2. It is first noted during the second week after a dose and is manifested by elevations in BUN and creatinine, serum uric acid and/or a decrease in creatinine clearance. Renal toxicity becomes more prolonged and severe with repeated courses of the drug. Measure serum creatinine, blood urea nitrogen, creatinine clearance, and serum electrolytes including magnesium prior to initiating therapy, and as clinically indicated. Consider magnesium supplementation as clinically needed. Renal function must return to normal before another dose of cisplatin can be given.
Renal function impairment has been associated with renal tubular damage. The administration of cisplatin with a 6-8 hour infusion with intravenous hydration and mannitol diuresis has been used to reduce nephrotoxicity. However, renal toxicity still can occur after utilization of these procedures.
Patients with baseline renal impairment, geriatric patients, patients who are taking other nephrotoxic drugs, or patients who are not well hydrated may be more susceptible to nephrotoxicity.
Consider alternative treatments or reduce the dose of cisplatin injection for patients with baseline renal impairment or who develop significant reductions in creatinine clearance during treatment with cisplatin injection according to clinical treatment guidelines.
Aminoglycoside antibiotics, when given concurrently or within 1-2 weeks after cisplatin administration, may potentiate its nephrotoxic effects (see 9.4 Drug-Drug Interactions). The renal toxicity of ifosfamide may be greater when used with cisplatin or in patients who have previously been given cisplatin.
Cisplatin may reduce the elimination of predominantly renal eliminated substances and enhance their toxicity. Reduction of the lithium blood levels was noticed in a few cases after treatment with cisplatin combined with bleomycin and etoposide. It is therefore recommended to monitor the lithium values.
Hyperuricemia has been reported to occur at approximately the same frequency as increases in BUN and serum creatinine. It is more pronounced after doses greater than 50 mg/m2, and peak levels of uric acid generally occur between 3 to 5 days after the dose. Allopurinol therapy for hyperuricemia effectively reduces uric acid levels.
Reproductive Health: Female and Male Potential
Verify the pregnancy status of females of reproductive potential prior to initiation of cisplatin. Women of childbearing potential should use effective contraception during treatment with cisplatin and for at least 29 weeks (7 months) following the last dose. Abnormal spermatogenesis and azoospermia have been reported. Men with female partners of childbearing potential should be advised to use effective contraception during treatment with cisplatin and for at least 17 weeks (4 months) after the last dose.
Fertility
Cisplatin can cause abnormal spermatogenesis and azoospermia in male patients (see 7 WARNINGS AND PRECAUTIONS and 8 ADVERSE REACTIONS). Although the impairment of spermatogenesis can be reversible, males undergoing cisplatin treatment should be warned about the possible adverse effects on male fertility. Therefore, males receiving cisplatin must always be advised to use a condom during any sexual contacts with females of child-bearing potential. Patients should not donate semen while taking cisplatin and up to 2 years after. Patients should receive genetic counselling for increased risk for conception prior to cisplatin therapy and up to 2 years after initial treatment. If a pregnancy occurs in a partner of a male patient taking cisplatin, it is recommended to refer the female partner to a genetic counselling for evaluation and advice.
Based on non-clinical and clinical findings, female fertility may be compromised by treatment with cisplatin. Use of cisplatin has been associated with cumulative dose-dependent ovarian failure, premature menopause and reduced fertility.
Both men and women should seek advice on fertility preservation before treatment.
Respiratory, thoracic and mediastinal disorders
Pulmonary embolism (including fatalities) has been reported. Pulmonary toxicity has been reported in patients treated with cisplatin in combination with bleomycin or 5-fluorouracil.
7.1 Special Populations
7.1.1 Pregnant Women
Cisplatin can cause fetal harm when administered to a pregnant woman. Cisplatin is mutagenic in bacteria, produces chromosome aberrations in animal cells in tissue culture and is teratogenic and embryotoxic in mice. Patients should be advised to avoid becoming pregnant. If this drug is used during pregnancy or if the patient becomes pregnant while taking this drug, the patient should be apprised of the potential hazard to the fetus (see 7 WARNINGS AND PRECAUTIONS, Carcinogenesis and Mutagenesis).
7.1.2 Breast-feeding
Cisplatin and its active metabolites have been identified in human milk of treated mothers. Patients receiving cisplatin should not breastfeed during treatment and for 1 month following last dose of treatment. Treatment should be discontinued or stopped taking into account the importance of the drug to the patient.
7.1.3 Pediatrics
Ototoxicity, which is significant and may be more pronounced in children, is manifested by tinnitus and/or loss of high frequency hearing and occasionally deafness. Cases of delayed-onset hearing loss have been reported in the pediatric population. Long term follow-up in this population is recommended. Since ototoxicity is cumulative, audiometric testing should be performed prior to initiating therapy and prior to each subsequent dose of drug (see 7 WARNINGS AND PRECATIONS – Ear/Nose/Throat).
7.1.4 Geriatrics
Geriatric patients, patients with baseline renal impairment, patients who are taking other nephrotoxic drugs, or patients who are not well hydrated may be more susceptible to nephrotoxicity (see 7 WARNINGS AND PRECAUTIONS – Renal). Geriatric patients may be more susceptible to myelosuppression (see 7 WARNINGS AND PRECAUTIONS – Hematologic). Geriatric patients may be more susceptible to peripheral neuropathy (see 7 WARNINGS AND PRECAUTIONS – Neurologic).
8 ADVERSE REACTIONS
The most frequently reported undesirable effects after cisplatin (> 10%) were hematological (leukopenia, thrombocytopenia and anemia), gastrointestinal (anorexia, nausea, vomiting and diarrhea), ear diseases (impaired hearing), kidney diseases (kidney failure, nephrotoxicity, hyperuricaemia and fever).
Toxic kidney, bone marrow and ear damage has been reported in up to one third of the patients after one single dose of cisplatin. The undesirable effects are generally dose-related and cumulative. Ototoxicity may be more severe in children.
The following serious adverse reactions have been reported (see 7 WARNINGS AND PRECAUTIONS):
- Secondary acute leukemia (see 7 WARNINGS AND PRECAUTIONS – Carcinogenesis and Mutagenesis)
- Thromboembolic events (see 7 WARNINGS AND PRECAUTIONS – Cardiovascular)
- Ototoxicity (see 7 WARNINGS AND PRECAUTIONS – Ear/Nose/Throat)
- Nausea and vomiting (see 7 WARNINGS AND PRECAUTIONS – Gastrointestinal)
- Myelosuppression (see 7 WARNINGS AND PRECAUTIONS – Hematologic)
- Hypersensitivity reactions (see 7 WARNINGS AND PRECAUTIONS – Immune)
- Infections and sepsis: (see 7 WARNINGS AND PRECAUTIONS – Infections and infestations)
- Neurotoxicity (see 7 WARNINGS AND PRECAUTIONS – Neurologic)
- Ocular toxicities (see 7 WARNINGS AND PRECAUTIONS – Ocular toxicities)
- Extravasation (see 7 WARNINGS AND PRECAUTIONS – Other toxicities)
- Renal toxicity/nephrotoxicity (see 7 WARNINGS AND PRECAUTIONS – Renal)
- Pulmonary embolism (see 7 WARNINGS AND PRECAUTIONS – Respiratory)
The following undesirable effects were seen in the clinical studies with cisplatin injection and post-marketing. Frequency is defined as follows: very common (≥ 1/10), common (≥ 1/100 to < 1/10), uncommon (≥ 1/1,000 to < 1/100), rare (≥ 1/10,000 to ≤ 1/1,000, very rare (≤ 1/10,000) and frequency not known (cannot be calculated from the available data).
| Investigations | |
|---|---|
| Rare | Increased serum amylase, reduced albumin levels. |
| Very rare | Increased iron concentrations. |
| Cardiac disorders | |
| Common | Heart rhythm disturbances, including bradycardia and tachycardia, and other changes in the ECG e.g. ST segment changes, ischaemic symptoms*. |
| Rare | Myocardial infarction. |
| Very rare | Cardiac arrest. |
| Frequency not known | Heart disease. |
| Neoplasms benign, malignant and unspecified (incl. cysts and polyps) | |
| Rare | Acute leukaemia. |
| Blood and lymphatic system disorders | |
| Very common | Bone marrow failure, thrombocytopaenia, leukopenia and anaemia. |
| Rare | Coombs positive haemolytic anaemia, severe bone marrow suppression (including agranulocytosis, aplastic anaemia). |
| Rare-very rare | Thrombotic microangiopathy (haemolytic uraemic syndrome). |
| Frequency not known | Neutropenia. |
| Nervous system disorders | |
|---|---|
| Common | Neurotoxicity characterized by e.g. peripheral neuropathy (typically bilateral and sensory). |
| Uncommon | Neurotoxic symptoms (tremor, muscle weakness, autonomous neuropathy, myelopathy, Lhermitte's syndrome, optical neuritis, seizures). |
| Rare | Cerebrovascular event, loss of the sense of touch, loss of the sense of taste, cerebral arteritis, encephalopathy, occlusion of the carotid artery, cerebral dysfunction (confusion, slurred speech, memory loss, paralysis), leukoencephalopathy and reversible posterior leukoencephalopathy syndrome. |
| Very rare | Unilateral retrobulbar neuritis with loss of visual acuity. |
| Frequency not known | Cerebral haemorrhage, loss of the sense of taste caused by an ischaemic stroke. |
| Eye disorders | |
| Uncommon | Acquired colour blindness, papilledema. |
| Rare | Cortical blindness. |
| Rare-very rare | Varying degrees of loss of vision. |
| Frequency not known | Blurry vision, optical neuritis, pigmentation of the retina. |
| Ear and labyrinth disorders | |
| Very common | Ototoxicity, tinnitus, hearing loss. |
| Common | Deafness, vestibular toxicity. |
| Gastrointestinal disorders | |
| Very common | Vomiting, nausea, loss of appetite, diarrhea. |
| Rare | Oral mucositis, stomatitis. |
| Frequency not known | Anorexia, hiccups. |
| Renal and urinary disorders | |
| Very common | Disrupted kidney function. |
| Common – very common | Tubular necrosis. |
| Frequency not known | Acute kidney failure, kidney failure (including an increase in blood urea and creatinine, serum uric acid and/or a drop in creatinine clearance), renal tubular disease. |
| Skin and subcutaneous tissue disorders | |
|---|---|
| Uncommon | Alopecia. |
| Frequency not known | Rash. |
| Musculoskeletal and connective tissue disorders | |
| Frequency not known | Muscle cramps, myalgia. |
| Endocrine disorders | |
| Uncommon | Hypersecretion of vasopressin (SIADH/Schwartz-Bartter syndrome). |
| Frequency not known | Elevated amylase in the blood |
| Metabolism and nutrition disorders | |
| Very common | Hyponatremia. |
| Common – very common | Hyperuricaemia. |
| Uncommon | Hypomagnesaemia, hypokalemia, hypophosphatemia, hypocalcaemia. |
| Rare | Tetany. |
| Frequency not known | Dehydration. |
| Infections and infestations | |
| Common | Sepsis. |
| Frequency not known | Infections (which may be fatal). |
| Vascular disorders | |
| Common | Venous thromboembolism. |
| Rare | Hypertension. |
| Rare – very rare | Raynaud's syndrome. |
| Very rare | Vascular disorders (cerebral or coronary ischemia, reduction of peripheral circulation related to Raynaud's syndrome). |
| Frequency not known | Thrombotic microangiopathy (hemolytic uraemic syndrome). |
| General disorders and administration site conditions | |
| Very common | Fever. |
| Common | Local oedemas, pain and erythema, necrosis and ulceration of the skin and phlebitis at the injection site. |
| Rare – very rare | Extravasation at the administration site with soft tissue injuries such as cellulitis and fibrosis. |
| Frequency not known | Fatigue, malaise. |
|---|---|
| Immune system disorders | |
| Uncommon | Allergic reactions may occur such as a rash, urticaria, erythema or pruritus. Anaphylactoid reactions (hypotension, tachycardia, dyspnoea, bronchospasm, wheezing breathing, facial oedema and fever have been reported). |
| Frequency not known | Flushing. |
| Hepatobiliary disorders | |
| Common | Reversible reduced liver function with an increase in liver enzymes and in the amount of bilirubin in the blood. |
| Respiratory, thoracic and mediastinal disorders | |
| Frequency not known | Lung embolism, pulmonary toxicity (in combination with bleomycin or 5-fluorouracil). |
| Reproductive system and breast disorders | |
| Uncommon | Disruption of spermatogenesis, ovulation disturbances, painful gynecomastia. |
| Frequency not known | Azoospermia. |
| *Has been reported especially when combined with other cytostatic drugs. | |
9 DRUG INTERACTIONS
9.2 Drug Interactions Overview
Cisplatin is usually combined with other cytostatic drugs with similar mechanisms of action. Additive toxicity may occur in such situations.
Concomitant use of bone marrow-suppressing drugs or radiation will enhance cisplatin’s bone marrow suppressive effect.
9.4 Drug-Drug Interactions
- Anticonvulsant agents: Plasma levels of anticonvulsants may become subtherapeutic during cisplatin therapy. In a randomized trial in advanced ovarian cancer, response duration was adversely affected when pyridoxine was used with altretamine (hexamethylmelamine) and cisplatin. In patients receiving cisplatin and phenytoin, serum concentrations of the latter may be decreased, possibly as a result of decreased absorption and/or increased metabolism. Absorption of carbamazepine and valproate sodium has also been reported to be impaired. Adequate plasma level monitoring of anticonvulsants is essential during cisplatin therapy.
- Nephrotoxic drugs: Aminoglycoside antibiotics, when given concurrently or within 1-2 weeks after cisplatin administration, may potentiate its nephrotoxic effects (see 7 WARNINGS AND PRECAUTIONS). The renal toxicity of ifosfamide may be greater when used with cisplatin or in patients who have previously been given cisplatin.
- Renally excreted drugs: Literature data suggest that cisplatin may reduce the elimination of predominantly renal eliminated substances and enhance their toxicity. Reduction of the lithium blood levels was noticed in a few cases after treatment with cisplatin combined with bleomycin and etoposide. It is therefore recommended to monitor the lithium values.
- Ototoxic drugs: Concurrent and/or sequential administration of ototoxic drugs such as aminoglycoside antibiotics or loop diuretics may increase the potential of cisplatin to cause ototoxicity, especially in the presence of renal impairment (see 7 WARNINGS AND PRECAUTIONS). Ifosfamide may increase hearing loss due to cisplatin.
- Anticoagulants: It is necessary to check the INR when oral anticoagulants such as coumarins/warfarin are used simultaneously with cisplatin.
- Paclitaxel: Administration of cisplatin prior to an infusion with paclitaxel may increase exposure to paclitaxel by 33% and can therefore intensify neutropenia and neurotoxicity (see 3 SERIOUS WARNINGS AND PRECAUTIONS BOX).
9.5 Drug-Food Interactions
Interactions with food have not been established.
9.6 Drug-Herb Interactions
Interactions with herbal products have not been established.
9.7 Drug-Laboratory Test Interactions
Interactions with laboratory tests have not been established.
10 CLINICAL PHARMACOLOGY
10.1 Mechanism of Action
Cisplatin has biochemical properties similar to those of bifunctional alkylating agents producing inter-strand and intra-strand cross-links in DNA. It is apparently not cell-cycle specific. The main mechanism of the cytotoxic action involves the binding of cisplatin to genomic DNA in the cell nucleus to form interstrand and intrastrand cross-links. This interferes with normal transcription and/or DNA replication mechanisms and triggers cytotoxic processes that lead to cell death. Antitumor activity of cisplatin was first demonstrated against sarcoma 180 and L1210 leukemia.
10.2 Pharmacodynamics
Cisplatin causes immunosuppression, which is short-lived (18-72 hours) and followed by a rapid increase in host immune response. This increase in the host immune response has been postulated to cause tumor regression in animals.
Subsequent investigations have shown significant activity of cisplatin IP as single agent in several experimental tumors, as follows:
- 1. Transplantable animal tumors, including Walker 256 carcinosarcoma, Dunning ascitic leukemia, Lewis lung carcinoma, Ehrlich ascites tumor, P-388 leukemia, B-16 melanoma, and the intracerebrally implanted ependymoblastoma tumor in mice.
- 2. Chemically-induced primary tumors, including the 7,12-di-methylbenzanthracene (DMBA)- induced mammary tumors in rats and the N-[4-(5-nitro-2-furyl)-2- thiazolyl] formamide (FANFT)-induced murine bladder cancer.
- 3. The virally-induced Rous sarcoma.
Cisplatin has demonstrated synergism in activity against L1210 leukemia when combined with other chemotherapeutic agents including cyclophosphamide, ICRF-159, ifosfamide, cytosine arabinoside, hydroxyurea, phosphoramide mustard, azacytidine, 5-fluorouracil, emetine, adriamycin and methotrexate. No apparent synergism was noted with BCNU.
10.3 Pharmacokinetics
Administration and Distribution:
Following bolus injection or intravenous infusion over 2 to 7 hours, of doses ranging from 50 to 100 mg/m2, plasma cisplatin half-life is approximately 30 minutes. The ratios of cisplatin to total, free (ultrafilterable) platinum in the plasma range from 0.4 to 1.1 after a dose of 100 mg/m2. After a single intravenous injection of cisplatin in dogs, the rapid-phase half-time was less than one hour and the slow-phase half-time was approximately 5 days. Approximately 60-70% of the dose was recovered in the urine in the first four hours after treatment (2).
Cisplatin does not undergo instantaneous and reversible binding to plasma proteins characteristic of normal drug-protein binding. However, the platinum from cisplatin becomes bound to plasma proteins. These complexes are slowly eliminated with a half-life of 5 days or more.
Cisplatin was distributed in highest concentrations in kidney, liver, gonads, spleen and adrenals at early times (1- 2 hours) after intravenous injection into dogs, but remained significantly elevated only in kidney, liver, ovary and uterus for up to six days post- treatment. The tissue:plasma ratio of platinum was 3:1 and 4:1 for liver and kidney, respectively, at 6 days post-treatment (2).
Following cisplatin doses of 20 to 120 mg/m2, the concentrations of platinum are highest in liver, prostate and kidney, somewhat lower in bladder, muscle, testicle, pancreas and spleen and lowest in bowel, adrenal, heart, lung, cerebrum and cerebellum. Platinum is present in tissues for as long as 180 days after the last administration. With the exception of intracerebral tumors, platinum concentrations in tumors are generally somewhat lower than the concentrations in the organ where the tumor is located. Different metastatic sites in the same patient may have different platinum concentrations. Hepatic metastases have the highest platinum concentrations, but these are similar to the platinum concentrations in the normal liver.
Elimination:
Over a range of doses administered as bolus injections or infusions of up to 24 hours, approximately 10 to 40% of the platinum administered is excreted in the urine in 24 hours. Similar mean urinary recoveries of platinum are found following daily administration of five consecutive days. Intact cisplatin accounts for the majority of platinum excreted in the urine within one hour of administration. Renal clearance of cisplatin exceeds creatinine clearance. The renal clearance of free (ultrafilterable) platinum also exceeds creatinine clearance. Renal clearance is non-linear and depends on dose, urine flow rate and individual variability in tubular secretion and reabsorption. No close correlation exists between the renal clearance of either free (ultrafilterable) platinum or cisplatin and creatinine clearance. There is a potential for accumulation of free (ultrafilterable) platinum in plasma when cisplatin is administered on a daily basis, but not when it is administered on an intermittent basis.
Although small amounts of platinum are present in the bile and large intestine after administration of cisplatin, fecal excretion of platinum appears to be insignificant.
11 STORAGE, STABILITY AND DISPOSAL
Unopened vials of Cisplatin Injection are stored at room temperature between 15 °C and 25 °C. Do not refrigerate or freeze cisplatin solutions since a precipitate will form. Protect from light.
12 SPECIAL HANDLING INSTRUCTIONS
- 1. Preparation of Cisplatin Injection should be done in a vertical laminar flow hood (Biological Safety Cabinet – Class II).
- 2. Cisplatin is cytotoxic. Personnel preparing Cisplatin Injection should wear PVC gloves, safety glasses, disposable gowns, and masks.
- 3. All needles, syringes, vials and other materials which have come in contact with Cisplatin Injection should be segregated and incinerated at 1000 °C or more. Sealed containers may explode if tightly sealed. Intact vials should be returned to the manufacturer for destruction. Proper precautions should be taken in packaging these materials for transport.
- 4. Personnel regularly involved in the preparation and handling of Cisplatin Injection should have bi-annual blood examinations.
PART II: SCIENTIFIC INFORMATION
13 PHARMACEUTICAL INFORMATION
Drug Substance
| Proper Name: | Cisplatin |
|---|---|
| Chemical Name: |
|
| Molecular formula and molecular mass: | Pt N2H6Cl2, 300.06 g/mol |
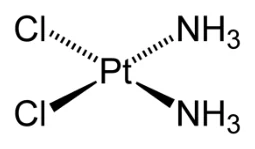
| Structural formula: | |
| Physiochemical properties: | Cisplatin is a heavy metal complex containing a central atom of platinum, surrounded by two chlorine atoms and two ammonia molecules in the cis position. It occurs as a fine yellow powder and is soluble in dimethylacetamide to an extent of 1% maximum. |
14 CLINICAL TRIALS
This information is not available for this drug product.
15 MICROBIOLOGY
No microbiological information is required for this drug product.
 |
16 NON-CLINICAL TOXICOLOGY
General Toxicology:
Toxicological Parameters of Cisplatin
Intravenous Route
Mice Single Dose | Dogs | Monkeys OD x 5 days | |||||||||||||||||||
|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|
| Single Dose | OD x 5 days | ||||||||||||||||||||
| mg/kg | mg/m2 | mg/kg | mg/m2 | mg/kg | mg/m2 | mg/kg | mg/m2 | ||||||||||||||
Highest non-toxic dose (HNTD) | -- | -- | 0.625 | 13.2 | 0.187 | 3.75 | 0.156 | 1.94 (or less) | |||||||||||||
| Toxic dose low (TDL) | -- | -- | 1.25 | 22.5 | 0.375 | 7.75 | 0.313 | 8.0 | |||||||||||||
| Toxic dose high (TDH) | -- | -- | 2.5 | 47.3 | 0.75 | 14.9 | 1.25 | 15.9 | |||||||||||||
| Lethal dose (LD) | -- | -- | 5.0 | 105.7 | 1.5 | 31.1 | 2.5 | 33.6 | |||||||||||||
| LD50 | 13.38 | 40.15 | -- | -- | -- | -- | -- | -- | |||||||||||||
Acute Toxicity
At lethal dose or LD50, death occurred in mice, dogs and monkeys within 2 to 8 days. Dogs showed severe, mostly hemorrhagic enterocolitis, severe or marked hypoplasia of the bone marrow, moderate or marked hypocellularity of the lymphoid tissues, marked or moderate renal tubular necrosis, together with azotemia, marked or moderate necrosis of the peripancreatic and omental fat tissue and pancreatitis. Monkeys exhibited severe enterocolitis or colitis, severe atrophy of the lymphoid tissues and moderate to severe hypoplasia of the bone marrow. One of the two monkeys furthermore exhibited severe nephrosis, marked focal myocardial necrosis, myocarditis, severe pancreas atrophy and marked atrophy of prostatic gland and testes.
Subacute Toxicity
Surviving dogs and monkeys showed reversible toxic signs, including dose-related emesis, anorexia, dehydration, weakness, leukocytosis, anemia, hypochloremia, proteinuria and appearance of leukocytes, erythrocytes and casts in the urine. Monkeys showed temporary azotemia and sporadic elevation of the transaminases.
Toxic signs disappeared within two weeks following treatment, and dogs and monkeys did not exhibit histopathology after an observation period from 61 to 129 days, with the exception of one dog that showed marked atrophy of the prostatic gland and one monkey that exhibited possible drug- related interstitial nephritis.
Mutagenicity
Cisplatin has been shown to be mutagenic in E. coli after prolonged cultivation of cells with sublethal levels of cisplatin.
Chromosome aberrations were observed in Chinese hamster bone marrow cells after an 8 mg/kg treatment of cisplatin.
In the Ames test, cisplatin was shown to be a mild to moderate mutagen.
Non-clinical findings in mice treated with cisplatin (5 mg/kg intraperitoneally) showed that cisplatin caused direct damage to primordial follicle oocytes, leading to apoptosis.
17 SUPPORTING PRODUCT MONOGRAPHS
PrCISPLATIN INJECTION BP (cisplatin solution, 1 mg/mL), submission control 275069, Product Monograph, Pfizer Canada ULC. (OCT 24, 2023)