


Product Monograph - Clarus
RECENT MAJOR LABEL CHANGES
| 7 WARNINGS AND PRECAUTIONS, Reproductive Health: Female and Male Potential, Function | 2025-12 |
|---|---|
| 7 WARNINGS AND PRECAUTIONS, Musculoskeletal | 2025-12 |
TABLE OF CONTENTS
Certain sections or subsections that are not applicable at the time of the preparation of the most recent authorized product monograph are not listed.
RECENT MAJOR LABEL CHANGES ............................................................................................. 2
TABLE OF CONTENTS ............................................................................................................... 2
PART I: HEALTH PROFESSIONAL INFORMATION ....................................................................... 4
1 INDICATIONS ................................................................................................................ 4
1.1 Pediatrics .......................................................................................................... 4
1.2 Geriatrics .......................................................................................................... 4
2 CONTRAINDICATIONS .................................................................................................. 5
3 SERIOUS WARNINGS AND PRECAUTIONS BOX ............................................................. 5
4 DOSAGE AND ADMINISTRATION .................................................................................. 7
4.1 Dosing Considerations ...................................................................................... 7
4.2 Recommended Dose and Dosage Adjustment ................................................. 7
4.4 Administration ................................................................................................. 8
4.5 Missed Dose ..................................................................................................... 8
5 OVERDOSAGE ............................................................................................................... 8
6 DOSAGE FORMS, STRENGTHS, COMPOSITION AND PACKAGING .................................. 9
7 WARNINGS AND PRECAUTIONS ................................................................................... 9
7.1 Special Populations ........................................................................................ 17
7.1.1 Pregnant Women ........................................................................................... 17
7.1.2 Breast-feeding ................................................................................................ 18
7.1.3 Pediatrics ........................................................................................................ 18
7.1.4 Geriatrics ........................................................................................................ 18
8 ADVERSE REACTIONS ................................................................................................. 19
8.1 Adverse Reaction Overview ........................................................................... 19
8.2 Clinical Trial Adverse Reactions ...................................................................... 19
8.4 Abnormal Laboratory Findings: Hematologic, Clinical Chemistry, and Other Quantitative Data ............................................................................................................ 21
8.5 Post-Market Adverse Reactions ...................................................................... 21
9 DRUG INTERACTIONS ................................................................................................. 21
9.2 Drug Interactions Overview ........................................................................... 21
9.3 Drug-Behavioural Interactions ....................................................................... 21
9.4 Drug-Drug Interactions ................................................................................... 22
9.5 Drug-Food Interactions .................................................................................. 22
9.6 Drug-Herb Interactions .................................................................................. 22
9.7 Drug-Laboratory Test Interactions .................................................................. 23
10 ACTION AND CLINICAL PHARMACOLOGY .................................................................. 23
10.1 Mechanism of Action ..................................................................................... 23
10.2 Pharmacodynamics ........................................................................................ 23
10.3 Pharmacokinetics ........................................................................................... 23
11 STORAGE, STABILITY AND DISPOSAL ......................................................................... 25
12 SPECIAL HANDLING INSTRUCTIONS ........................................................................... 25
PART II: SCIENTIFIC INFORMATION ........................................................................................ 26
13 PHARMACEUTICAL INFORMATION ............................................................................ 26
14 CLINICAL TRIALS ........................................................................................................ 26
14.2 Comparative Bioavailability Studies ............................................................... 26
15 MICROBIOLOGY ......................................................................................................... 28
16 NON-CLINICAL TOXICOLOGY ...................................................................................... 28
17 SUPPORTING PRODUCT MONOGRAPHS ..................................................................... 32
PATIENT MEDICATION INFORMATION ................................................................................... 33
PART I: HEALTH PROFESSIONAL INFORMATION
1 INDICATIONS
CLARUS® (isotretinoin) is indicated for the treatment of:
- Severe Nodular and/or Inflammatory Acne
- Acne Conglobata
- Recalcitrant Acne
Because of significant side effects associated with its use, CLARUS® should be reserved for patients where the conditions listed above are unresponsive to conventional first line therapies.
CLARUS® should only be prescribed by physicians knowledgeable in the use of retinoids systemically, who understand the risk of teratogenicity in females of child bearing age and who are experienced in counselling young adults for whom isotretinoin is generally indicated (see 2 CONTRAINDICATIONS, 3 SERIOUS WARNINGS AND PRECAUTIONS BOX and 7.1.1 Pregnant Women).
A careful assessment of the patient’s mental state should be made, including whether or not they have a history of previous psychiatric illness (see 3 SERIOUS WARNINGS AND PRECAUTIONS BOX, Psychiatric).
It is strongly recommended that each CLARUS® prescription be limited to a one-month supply in order to encourage patients to return for follow-up to monitor side-effects.
The pharmacist must ensure that:
- Prescriptions of CLARUS® for women of child-bearing potential should be limited to 30 days of treatment and continuation of treatment requires a new prescription. Ideally, pregnancy testing, issuing a prescription and dispensing of CLARUS® should occur on the same day.
- Dispensing of CLARUS® should occur within a maximum of 7 days of the prescription.
1.1 Pediatrics
<12 years of age: The use of CLARUS® in pediatric patients less than 12 years of age is not recommended (see 7.1.3 Pediatrics).
12 to 17 years of age: The use of CLARUS® for the treatment of severe recalcitrant nodular acne in pediatric patients ages 12 to 17 years should be given careful consideration, especially for those patients where a known metabolic or structural bone disease exists (see 7.1.3 Pediatrics).
1.2 Geriatrics
> 65 years of age: Clinical studies of isotretinoin did not include sufficient numbers of subjects aged 65 years and over to determine whether they respond differently from younger subjects. Although reported clinical experience has not identified differences in responses between elderly and younger patients, effects of aging might be expected to increase some risks associated with isotretinoin therapy (see 7.1.4 Geriatrics)
2 CONTRAINDICATIONS
CLARUS® (isotretinoin) is contraindicated in pregnancy.
- Females must not become pregnant while taking CLARUS® or for at least one month after its discontinuation. Isotretinoin causes severe birth defects in a very high percentage of infants born to women who became pregnant during treatment with isotretinoin in any amount, even for a short period of time. Birth defects which have been documented following isotretinoin exposure include: CNS (hydrocephalus, hydranencephaly, microcephaly, posterior fossa abnormalities, cranial nerve dysfunction, cerebellar malformation); craniofacial (anotia, microtia, low set ears, small or absent external auditory canals, microphthalmia, facial dysmorphia, cleft palate); cardiac (septal defects, aortic arch abnormalities, tetralogy of Fallot); thymus gland abnormalities; and parathyroid hormone deficiency. Cases of IQ scores less than 85 with or without other abnormalities have been reported.
- Potentially any exposed fetus can be affected. There are no accurate means of determining whether an exposed fetus has been affected (see 7.1.1 Pregnant Women).
- If pregnancy does occur during treatment with CLARUS® or for one month after its discontinuation, CLARUS® treatment must be immediately stopped and the physician and patient should discuss the desirability of continuing the pregnancy.
- CLARUS® should only be prescribed by physicians knowledgeable in the use of retinoids systemically (see 1 INDICATIONS).
CLARUS® is also contraindicated in the following conditions:
- breastfeeding women,
- hepatic and renal insufficiency,
- hypervitaminosis A,
- patients with excessively elevated blood lipid values,
- patients taking tetracyclines (see 3 SERIOUS WARNINGS AND PRECAUTIONS BOX and 9.4 Drug-Drug Interactions).
- patients who are sensitive to isotretinoin, or to any of the excipients. CLARUS® capsules contain ammonium hydroxide, beeswax yellow, gelatin, glycerin, hydrogenated vegetable oil, isopropyl alcohol, lecithin, medium chain triglyceride, polyethylene glycol, polyvinyl acetate phthalate, propylene glycol, red iron oxide, SDA 35A alcohol, soybean oil, synthetic black iron oxide, titanium dioxide and yellow iron oxide (see 6 DOSAGE FORMS, STRENGTHS, COMPOSITION AND PACKAGING). CLARUS® does not contain peanut oil.
3 SERIOUS WARNINGS AND PRECAUTIONS BOX
The Information/Consent/Agreement should be signed by all patients prior to starting therapy with CLARUS®. This consent form is designated to ensure that patients have been counselled on and understand the psychiatric and teratogenic risks associated with isotretinoin, prior to starting treatment. The consent form can be obtained by downloading it from the CLARUS® CLEARTM Program Website, www.clarusclearprogram.ca, or by contacting Customer Service centre at customerservice@mylan.ca.
Serious Warnings and Precautions
All patients must sign the informed consent form prior to initiating therapy.
Pregnancy Prevention: Isotretinoin is a known teratogen contraindicated in pregnancy (see boxed 2 CONTRAINDICATIONS). Physicians should only prescribe CLARUS® to females of childbearing potential if ALL the conditions described below under “Conditions of use” are met.
In addition, when prescribing this drug to female patients of childbearing potential, physicians must use Mylan Pharmaceuticals ULC’s CLinical Education and Awareness Resource (CLEARTM), which includes the following:
- comprehensive information about the potential risks of this drug
- a checklist for criteria which must be met prior to prescribing this drug to female patients of childbearing potential
- detailed information on birth control options
- a patient informed consent for review and signature
- monthly pregnancy reminders for physicians to use at each patient visit during the treatment period
Psychiatric: Some patients treated with isotretinoin have become depressed and some attempted or died by suicide. Although a causal relationship has not been established, all patients should be screened and monitored for signs of depression before and during therapy (see 7 WARNINGS AND PRECAUTIONS, Monitoring and Laboratory Tests). Physicians should determine whether the patient may be depressed or has a history of depression including a family history of major depression before starting therapy with CLARUS®. If symptoms of depression develop or worsen during treatment with CLARUS®, the drug should be discontinued promptly and the patient referred for appropriate psychiatric treatment as necessary. However, discontinuation of CLARUS® may not alleviate symptoms and therefore further psychiatric or psychological evaluation may be necessary.
A Psychiatric Screening Checklist is available to assist physicians in screening patients for depression/suicidality prior to treatment and in monitoring for the development of psychiatric symptoms during treatment.
The following materials are available to physicians and pharmacists. Please contact the Customer Service centre provided below.
- Pregnancy Prevention Checklist
- Information/Consent/Agreement
- Patient Monitoring Chart
- Blood Monitoring Guide
- CLEARTM Flowchart
- Patient Reminder Slips
- Psychiatric Screening Checklist
Mylan Pharmaceuticals ULC Customer Service:
85 Advance Road, Etobicoke, ON M8Z 2S6
Toll-Free: 1-844-596-9526
Toll-Free Fax: 1-888-745-7373
customerservice@mylan.ca
- Neurologic: Isotretinoin use has been associated with a number of cases of pseudotumor cerebri (benign intracranial hypertension), some of which involved concomitant use of tetracyclines (see 2 CONTRAINDICATIONS and 9.4 Drug-Drug Interactions). Early symptoms of pseudotumor cerebri include headache, nausea and vomiting, and visual disturbances. Patients with these symptoms should be screened for papilledema and, if present, the drug should be discontinued immediately and the patient referred to a neurologist for diagnosis and care. Concomitant treatment with tetracyclines should be avoided (see 2 CONTRAINDICATIONS and 9.4 Drug-Drug Interactions).
4 DOSAGE AND ADMINISTRATION
4.1 Dosing Considerations
Female patients of childbearing potential must not be given CLARUS® until pregnancy is excluded.
4.2 Recommended Dose and Dosage Adjustment
The therapeutic response to isotretinoin is dose-related and varies between patients. This necessitates individual adjustment of dosage according to the response of the condition and the patient’s tolerance of the drug. In most cases, complete or near-complete suppression of acne is achieved with a single 12 to 16 week course of therapy. If a second course of therapy is needed, it can be initiated eight or more weeks after completion of the first course, since experience has shown that patients may continue to improve while off the drug.
Initial Therapy
The initial dose of CLARUS® should be individualized according to the patient’s weight and severity of the disease.
In general, patients initially should receive CLARUS® 0.5 mg/kg body weight daily for a period of two to four weeks, when their responsiveness to the drug will usually be apparent. It should be noted that transient exacerbation of acne is occasionally seen during this initial period.
The daily dosage should be taken with food in the nearest number of whole capsules, either as a single dose or in two divided doses during the day, whichever is more convenient.
Maintenance Therapy
Maintenance dose should be adjusted between 0.1 and 1 mg/kg body weight daily and, in exceptional instances, up to 2 mg/kg body weight daily, depending upon individual patient response and tolerance to the drug.
A complete course of therapy consists of 12 to 16 weeks of CLARUS® administration.
Patients may show additional improvement for up to several months after a course of CLARUS® has been completed. With effective treatment, appearance of new lesions will not normally be evident for a period of at least three to six months.
4.4 Administration
CLARUS® is for oral use only.
CLARUS® should only be prescribed by physicians knowledgeable in the use of retinoids systemically, who understand the risk of teratogenicity in females of child bearing age and who are experienced in counselling young adults for whom isotretinoin is generally indicated (see 1 INDICATIONS and boxed 2 CONTRAINDICATIONS).
4.5 Missed Dose
If a patient misses a dose of CLARUS®, it may be taken later the same day, but, the patient should be instructed to not take more CLARUS® in one day than what has been prescribed. The patient should then administer the next dose on the usual scheduled dosing day. The patient should not take a double dose to make up for a missed dose.
5 OVERDOSAGE
In the event of acute CLARUS® overdose evacuation of the stomach should be considered during the first few hours after this overdose. Signs and symptoms of acute overdose have been associated with headache, vomiting, facial flushing, cheilitis, abdominal pain, dizziness and ataxia. To date, all symptoms have quickly resolved without apparent residual effects and usually without treatment. Elevated intracranial pressure has been reported with patients receiving therapeutic doses of isotretinoin. Patients with a CLARUS® overdose should be monitored closely for signs of increased intracranial pressure. Signs of hypervitaminosis A could appear in cases of overdose.
Limited data exists on the pharmacokinetic characteristics of isotretinoin in an overdose situation (10.3 Pharmacokinetics). Since it is difficult to extrapolate from the results of these studies to the overdose situation, the following precautions should be taken with all female patients of childbearing potential who have taken an overdose of CLARUS®.
- 1. At the time of the overdose, a pregnancy test must be performed and a blood sample collected for the determination of isotretinoin and metabolite concentrations.
- 2. One complete menstrual cycle after the overdose, a second pregnancy test must be performed and a second blood sample collected for the determination of isotretinoin and metabolite concentrations.
- 3. Effective contraception must be used for at least one complete menstrual cycle after the overdose and continued longer, if necessary until physiological plasma concentrations of isotretinoin and its major metabolites are reached.
Patients who present with a positive pregnancy test at the time of the overdose, one complete menstrual cycle after the overdose, or while isotretinoin or metabolite blood concentrations are measurable, should be fully counselled on the serious risk to the fetus from this exposure to isotretinoin and the physician and patient should discuss the desirability of continuing the pregnancy. (See 2 CONTRAINDICATIONS, 7.1.1 Pregnant Women and 16 NON-CLINICAL TOXICOLOGY, Reproduction and Teratology Studies).
Canadian Regional Poison Information Centres have been advised on the proper collection and handling of isotretinoin blood samples and also on the laboratory(s) equipped to assay these samples.
For the most recent information in the management of a suspected drug overdose, contact your regional poison control centre or Health Canada’s toll-free number, 1-844 POISON-X (1-844-764-7669).
6 DOSAGE FORMS, STRENGTHS, COMPOSITION AND PACKAGING
Table 1 - Dosage Forms, Strengths, Composition and Packaging
| Route of Administration | Dosage Form / Strength | Non-Medicinal Ingredients |
| Oral | Capsules / 10 mg | Ammonium hydroxide, beeswax yellow, gelatin, glycerin, hydrogenated vegetable oil, isopropyl alcohol, lecithin, medium chain triglyceride, polyethylene glycol, polyvinyl acetate phthalate, propylene glycol, red iron oxide, SDA 35A alcohol, soybean oil and synthetic black iron oxide |
| Oral | Capsules / 40 mg | Ammonium hydroxide, beeswax yellow, gelatin, glycerin, hydrogenated vegetable oil, isopropyl alcohol, lecithin, medium chain triglyceride, polyethylene glycol, polyvinyl acetate phthalate, propylene glycol, red iron oxide, SDA 35A alcohol, soybean oil, synthetic black iron oxide, titanium dioxide and yellow iron oxide |
Description
CLARUS® 10 mg capsule: An oval capsule with a yellow to orange paste fill and a reddish brown opaque gelatin shell, printed with black ink “I” logo on one side.
CLARUS® 40 mg capsule: An oval capsule with a yellow to orange paste fill and an orange brown opaque gelatin shell, printed with black ink “I 40” logo on one side.
CLARUS® 10 mg and 40 mg capsules are available in blister packages of 30 capsules.
7 WARNINGS AND PRECAUTIONS
Please see 3 SERIOUS WARNINGS AND PRECAUTIONS BOX.
General
Conditions of Use
- 1. The patient has severe disfiguring nodular and/or inflammatory acne, acne conglobata or recalcitrant acne that has not responded to standard therapy, including systemic antibiotics.
- 2. The patient is reliable in understanding and carrying out instructions.
- 3. All patients must sign the informed consent form prior to initiating therapy. This form is provided to the physician via the www.clarusclearprogram.ca website or by contacting Mylan Pharmaceuticals ULC Customer Service line at 1-844-596-9526.
CLARUS® is contraindicated in females of childbearing potential unless ALL of the following conditions apply:
- 4. The patient is able and willing to comply with the mandatory effective contraceptive measures.
- 5. The patient has received, and acknowledged understanding of, a careful oral and printed explanation of the hazards of fetal exposure to isotretinoin and the risk of possible contraception failure. This explanation may include showing a line drawing to the patient of an infant with the characteristic external deformities resulting from isotretinoin exposure during pregnancy.
- 6. The patient has been informed and understands the need to rapidly consult her physician if there is a risk of pregnancy.
- 7. The patient understands the need for rigorous follow-up on a monthly basis.
- 8. The patient uses effective contraception without any interruption for one month before beginning CLARUS® therapy, during CLARUS® therapy and for one month following discontinuation of CLARUS® therapy. It is recommended that two reliable forms of contraception be used simultaneously.
- 9. The patient has had two negative pregnancy tests before starting CLARUS® therapy with the first pregnancy test conducted at initial assessment when the patient is qualified for CLARUS® therapy by the physician. The patient has had a second serum or urine pregnancy test with a sensitivity of at least 25 mIU/mL with a negative result, performed in a licensed laboratory, within 11 days prior to initiating therapy. The patient has had two or three days of the next normal menstrual period before CLARUS® therapy is initiated.
- 10. In the event of relapse treatment, the patient must also use the same uninterrupted and effective contraceptive measures one month prior to, during and for one month after CLARUS®.
(For items 4 to 10 above, please see 7.1.1 Pregnant Women).
It is mandatory that all female patients of childbearing potential treated with CLARUS® have regular negative monthly pregnancy tests prior to receiving each 30-day CLARUS® prescription and an additional test one month after the discontinuation of treatment.
Even female patients who normally do not employ contraception due to a history of infertility, or claim absence of sexual activity should be advised to employ contraception while taking CLARUS®, following the above guidelines. Even female patients who have amenorrhea must follow all the advice on effective contraception unless the patient has undergone hysterectomy, bilateral oophorectomy, or has been medically confirmed to be postmenopausal.
Information concerning the CLEARTM program (see 3 SERIOUS WARNINGS AND PRECAUTIONS BOX) has also been provided directly to patients via the CLARUS® compliance packaging. This “Patient Information” asks female patients of childbearing potential, who have not been counselled using Mylan Pharmaceuticals ULC’s CLEARTM program, to contact their physician for further information. All patient materials and physician materials can be downloaded from the www.clarusclearprogram.ca website or by contacting Mylan Pharmaceuticals ULC Customer Service line at 1-844-596-9526.
Patients should also be informed that confidential contraception counselling (provided by a healthcare professional) is available from Mylan Pharmaceuticals ULC.
- Blood Donation
It is recommended that blood donation for transfusion purposes be deferred during therapy with CLARUS® and for one month after discontinuation of treatment. Theoretically, blood from such donors could present a small risk to the fetus if transfused to a pregnant mother during the first trimester of pregnancy.
Cardiovascular
Approximately 25% of patients receiving isotretinoin experienced an elevation in plasma triglycerides. Approximately 15% developed a decrease in high density lipoproteins and about 7% showed an increase in cholesterol levels. These effects on triglycerides, HDL and cholesterol were reversible upon reduction of the dose or cessation of isotretinoin therapy (see 8.2 Clinical Trial Adverse Reactions, Laboratory Abnormalities).
Patients with increased tendency to develop hypertriglyceridemia include those with diabetes mellitus, obesity, increased alcohol intake and familial history.
The cardiovascular consequences of hypertriglyceridemia are not well understood, but may increase the patient’s risk status. Therefore, every attempt should be made to control significant triglyceride elevation (see 7 WARNINGS AND PRECAUTIONS, Monitoring and Laboratory Tests). Some patients have been able to reverse triglyceride elevation by reduction in weight, restriction of dietary fat and alcohol, and reduction in dose while continuing isotretinoin. An obese male patient with Darier’s disease developed elevated triglycerides and subsequent eruptive xanthomas.
Ear/Nose/Throat
Impaired hearing at certain frequencies has been reported in some patients treated with isotretinoin. Patients who experience tinnitus or hearing impairment should discontinue
CLARUS® treatment and be referred for specialized care for further evaluation.
Endocrine and Metabolism
Patients with diabetes or a family history of diabetes may experience problems with the control of their blood sugar during CLARUS® therapy. Therefore, known or suspected diabetics should have periodic blood sugar determinations. Although no causal relationship has been established, elevated fasting blood sugars have been reported, and new cases of diabetes have been diagnosed during isotretinoin therapy (see 8.2 Clinical Trial Adverse Reactions, Laboratory Abnormalities).
Gastrointestinal
Isotretinoin has been temporally associated with inflammatory bowel disease (including regional ileitis, colitis and hemorrhage) in patients without a prior history of intestinal disorders. Patients experiencing abdominal pain, rectal bleeding or severe diarrhea should discontinue CLARUS® immediately.
Hepatic/Biliary/Pancreatic
Liver function tests should be monitored before treatment and at regular intervals during treatment (one month after the start of treatment and at least three month intervals thereafter) unless more frequent monitoring is clinically indicated. Several cases of clinical hepatitis have been noted which are considered to be possibly or probably related to isotretinoin therapy. Additionally, mild to moderate elevations of liver enzymes have been observed in approximately 15% of individuals treated during clinical trials, some of which normalized with dosage reduction or continued administration of the drug. If normalization does not readily occur, or if hepatitis is suspected during treatment with CLARUS®, the drug should be discontinued and the etiology further investigated (see 2 CONTRAINDICATIONS and 7 WARNINGS AND PRECAUTIONS, Monitoring and Laboratory Tests).
There have been some reports of acute pancreatitis, which is known to be potentially fatal. This is sometimes associated with elevation of serum triglycerides in excess of 800 mg/dL or 9 mmol/L (see 8.2 Clinical Trial Adverse Reactions, Laboratory Abnormalities). Therefore, every attempt should be made to control significant triglyceride elevation (see 7 WARNINGS AND PRECAUTIONS, Cardiovascular). CLARUS® should be discontinued if uncontrolled hypertriglyceridemia or symptoms of pancreatitis occur.
Immune
Anaphylactic reactions have been reported. These reactions were more serious after prior exposure to topical retinoids. Allergic cutaneous reactions and serious cases of allergic vasculitis, often with purpura (bruises and red patches) of the extremities and extracutaneous involvement have been reported. Severe allergic reactions necessitate interruption of therapy and careful monitoring.
Monitoring and Laboratory Tests
- Pregnancy Tests:
The patient should have two negative pregnancy tests (β-hCG in urine or serum) before starting CLARUS® therapy with the first pregnancy test conducted at initial assessment when the patient is qualified for CLARUS® therapy by the physician. The patient then should have a second pregnancy test with a sensitivity of at least 25 mIU/mL with a negative result, performed in a licensed laboratory, within 11 days prior to initiating therapy. The patient has had two or three days of the next normal menstrual period before CLARUS® therapy is initiated. Pregnancy test must be repeated monthly for pregnancy detection during CLARUS® treatment and at one month after discontinuation of treatment. The dates and results of the pregnancy tests should be documented.
The following tests are required before starting CLARUS®, at first month, then as clinically indicated:
Serum blood lipid determinations (under fasting conditions) should be performed before CLARUS® is given and then at intervals (one month after the start of therapy) until the lipid response to CLARUS® is established (which usually occurs within four weeks), and also at the end of treatment.
Complete blood count and differential: for early detection of leukopenia, neutropenia, thrombocytopenia and anemia.
Liver function tests: Increases in about 15% of ALT, AST, ALP baseline levels have been reported. Liver function tests should be monitored before treatment and at regular intervals during treatment (one month after the start of treatment and at least three month intervals thereafter) unless more frequent monitoring is clinically indicated.
Blood glucose levels: all patients and in particular patients with known or suspected diabetes should have periodic blood sugar determinations.
- Special Patient Groups:
In high risk patients (with diabetes, obesity, alcoholism or lipid metabolism disorder) undergoing treatment with CLARUS®, more frequent checks of serum values for lipids (see 7 WARNINGS AND PRECAUTIONS, Endocrine and Metabolism and Hepatic/Biliary/Pancreatic) and/or blood glucose may be necessary.
Musculoskeletal
Effects of multiple courses of isotretinoin on the developing musculoskeletal system are unknown. There is some evidence that long-term, high-dose, or multiple courses of therapy with isotretinoin have more of an effect than a single course of therapy on the musculoskeletal system (see 7.1.3 Pediatrics).
In an open-label clinical trial (N=217) of a single course of therapy with isotretinoin for severe recalcitrant nodular acne in pediatric patients 12 to 17 years, bone density measurements at several skeletal sites were not significantly decreased (lumbar spine change >-4% and total hip change>-5%) or were increased in the majority of patients. One patient had a decrease in lumbar spine bone mineral density >4% based on unadjusted data. Sixteen (7.9%) patients had decreases in lumbar spine bone mineral density >4%, and all the other patients (92%) did not have significant decreases or had increases (adjusted for body mass index). Nine patients (4.5%) had a decrease in total hip bone mineral density >5% based on unadjusted data. Twenty-one (10.6%) patients had decreases in total hip bone mineral density >5%, and all the other patients (89%) did not have significant decreases or had increases (adjusted for body mass index). Follow-up studies performed in 8 of the patients with decreased bone mineral density for up to 11 months thereafter demonstrated increasing bone density in 5 patients at the lumber spine, while the other 3 patients had lumbar spine bone density measurements below baseline values. Total hip bone mineral densities remained below baseline (range-1.6% to -7.6%) in 5 of 8 patients (62.5%).
In this clinical trial transient elevations in CPK were observed in 12% of patients, including those undergoing strenuous physical activity in association with reported musculoskeletal adverse events such as back pain, arthralgia, limb injury, or muscle sprain. In these patients, approximately half of the CPK elevations returned to normal within 2 weeks and half returned to normal within 4 weeks. No cases of rhabdomyolysis were reported in this trial.
In a separate open-label extension study of 10 patients, ages 13-18 years, who started a second course of isotretinoin 4 months after the first course, two patients showed a decrease in mean lumbar spine bone mineral density up to 3.25%.
Spontaneous reports of osteoporosis, osteopenia, bone fractures, and delayed healing of bone fractures have been seen in the isotretinoin population. While causality to isotretinoin has not been established, an effect cannot be ruled out. Longer term effects have not been studied. It is important that CLARUS® be given at the recommended doses for no longer than the recommended duration.
Although an effect of isotretinoin on bone loss is not established, physicians should use caution when prescribing CLARUS® to patients with a genetic predisposition for age-related osteoporosis, a history of childhood osteoporosis conditions, osteomalacia, or other disorders of bone metabolism. This would include patients diagnosed with anorexia nervosa and those who are on chronic drug therapy that causes drug-induced osteoporosis/osteomalacia and/or affects vitamin D metabolism, such as systemic corticosteroids and any anticonvulsant. Patients may be at increased risk when participating in sports with repetitive impact where the risks of spondylolisthesis with and without pars fractures and hip growth plate injuries in early and late adolescence are known. There are spontaneous reports of fractures and/or delayed healing in patients while on treatment with isotretinoin or following cessation of treatment with isotretinoin while involved in these activities. While causality to isotretinoin has not been established, an effect cannot be ruled out.
Myalgia and arthralgia (mild to moderate) may occur and may be associated with reduced tolerance to vigorous exercise (see 8.2 Clinical Trial Adverse Reactions, Musculoskeletal and 8.5 Post-Market Adverse Reactions, Musculoskeletal). Instances of raised serum creatine phosphokinase (CPK) values have been reported in patients receiving isotretinoin, particularly those undertaking vigorous physical activity. Discontinuation of CLARUS® may be required.
There have been post-marketing serious reports of rhabdomyolysis, often leading to hospitalization and some with fatal outcome, particularly in those undergoing strenuous physical activity. Patients should abstain from vigorous exercise activity during CLARUS® treatment (see 8.5 Post-Market Adverse Reactions).
Sacroiliitis has been reported in patients exposed to isotretinoin. To differentiate sacroiliitis from other causes of back pain, in patients with clinical signs of sacroiliitis, further evaluation may be needed including imaging modalities such as MRI. In cases reported post-marketing, sacroiliitis improved after discontinuation of isotretinoin and appropriate treatment.
- Hyperostosis
Due to possible occurrence of bone changes, a careful evaluation of the risk/benefit ratio should be carried out in every patient and CLARUS® administration should be restricted to severe cases of acne. Bone changes including, premature epiphyseal closure, hyperostosis and calcification of tendons and ligaments have occurred after several years of administration at high doses for treating disorders of keratinization. The dose levels, duration of treatment and total cumulative dose in these patients generally far exceeded those recommended for the treatment of acne.
In clinical trials of disorders of keratinization, with a mean dose of 2.24 mg/kg/day, a high prevalence of skeletal hyperostosis was noted. Two children showed x-ray findings suggestive of premature closure of the epiphysis. Additionally, skeletal hyperostosis was noted in six of eight patients in a prospective study of disorders of keratinization.
Minimal skeletal hyperostosis and calcification of tendons have also been observed by x-rays in prospective studies of cystic acne patients treated with a single course of therapy at recommended doses. There are spontaneous reports of premature epiphyseal closure in acne patients receiving recommended doses of isotretinoin. The effect of multiple courses of isotretinoin on epiphyseal closure is unknown.
In a clinical study of 217 pediatric patients (12 to 17 years) with severe recalcitrant nodular acne, hyperostosis was not observed after 16 to 20 weeks of treatment with approximately 1 mg/kg/day of isotretinoin given in two divided doses. Hyperostosis may require a longer time frame to appear. The clinical course and significance remain unknown.
Neurologic
Isotretinoin use has been associated with a number of cases of pseudotumor cerebri (benign intracranial hypertension), see 3 SERIOUS WARNINGS AND PRECAUTIONS BOX.
Ophthalmologic
Corneal opacities have occurred in patients receiving isotretinoin for acne and more frequently when higher drug dosages were used in patients with disorders of keratinization. Dry eyes, corneal opacities, decreased night vision, keratitis, blepharitis and conjunctivitis usually resolve after discontinuation of therapy. Due to the possible occurrence of keratitis, patients with dry eyes should be monitored. All CLARUS® patients experiencing visual difficulties should discontinue the drug and have an ophthalmological examination. (see 8.2 Clinical Trial Adverse Reactions, Ophthalmologic). Dry eyes, can be helped by the application of a lubricating eye ointment or by the application of tear replacement therapy. Intolerance to contact lenses may occur which may necessitate the patient to wear glasses during treatment.
A number of cases of decreased night vision have occurred during isotretinoin therapy and in rare instances have persisted after therapy (see 8.2 Clinical Trial Adverse Reactions, Ophthalmologic). Because the onset in some patients was sudden, patients should be advised of this potential problem and warned to be cautious when driving or operating any vehicle at night. CLARUS® patients experiencing visual impairment should discontinue treatment and have an ophthalmological examination. Visual problems should be carefully monitored.
Psychiatric
Some patients treated with isotretinoin have become depressed and some attempted or died by suicide, see 3 SERIOUS WARNINGS AND PRECAUTIONS BOX.
- Signs of Depression:
Sad mood, hopelessness, feeling of guilt, worthlessness or helplessness, loss of pleasure or interest in activities, fatigue, difficulty concentrating, changes in sleep pattern, change in weight or appetite, suicidal thoughts or attempts, restlessness, irritability, acting on dangerous impulses, and persistent physical symptoms unresponsive to treatment. If symptoms of depression develop or worsen during treatment with CLARUS®, the drug should be discontinued promptly and the patient referred for appropriate psychiatric treatment.
Renal
Renal insufficiency, see 2 CONTRAINDICATIONS.
Reproductive Health: Female and Male Potential
Contraception
Effective contraception must be used for at least one month before starting CLARUS® treatment, during treatment and for at least one month following the discontinuation of CLARUS® treatment.
Any birth control method can fail. Therefore, it is recommended that two reliable forms of contraception be used simultaneously (see 9.4 Drug-Drug Interactions). At least 1 of these forms of contraception must be a primary form, unless the patient has undergone a hysterectomy, bilateral oophorectomy, or has been medically confirmed to be postmenopausal. Effective forms of contraception include: primary forms which are tubal ligation, partner's vasectomy, intrauterine devices, birth control pills, and topical/injectable/insertable hormonal birth control products and secondary, or barrier forms of contraception which include diaphragms, latex condoms, and cervical caps. A diaphragm and cervical cap must each be used with a spermicide.
Teratogenic Risk
Pregnancy occurring during treatment with CLARUS® and for one month after its discontinuation carries the risk of fetal malformation and the increased risk of spontaneous abortion (see 2 CONTRAINDICATIONS and 16 NON-CLINICAL TOXICOLOGY, Reproduction and Teratology Studies). CLARUS® treatment must be stopped and the patient should be fully counselled on the serious risk to the fetus should they become pregnant while undergoing treatment. If pregnancy does occur during this time the physician and patient should discuss the desirability of continuing the pregnancy.
Function
Risk of Sexual Side Effects: Cases of sexual dysfunction including erectile dysfunction, decreased/loss of libido, vulvovaginal dryness, orgasm difficulties, and genital hypoaesthesia have been reported in patients with the use of isotretinoin. There have been reports of persistence of these events following drug discontinuation. While causality to isotretinoin could not be definitively established, an effect cannot be ruled out. When deciding on treatment with isotretinoin, patients, and where appropriate, parents or caregivers, should be informed about this potential risk. All patients should be screened and monitored, and advised to monitor themselves, for signs and symptoms of sexual dysfunction before and during therapy.
Male Patients
The available data suggest that the level of maternal exposure from the semen of the patients receiving isotretinoin is not of a sufficient magnitude to be associated with the teratogenic effects of isotretinoin. The threshold dose of isotretinoin exposure causing birth defects is not known. Post-marketing reports through 20 years include 4 with isolated defects compatible with features of retinoid exposed fetus; however, 2 of these reports were incomplete, and 2 had other possible explanations for the defects observed.
Male patients should be reminded that they must not share their medication with anyone, particularly not females.
Isotretinoin, in therapeutic dosages, does not affect the number, motility and morphology of sperm.
Both male and female patients should be given a copy of the Patient Medication Information.
Skin
Acute exacerbation of acne is occasionally seen during the initial period but this subsides with continued treatment, usually 7-10 days, and usually does not require dose adjustment.
Exposure to intense sunlight or to UV rays should be avoided. When necessary a sun-protection product with a high protection factor of at least SPF 15 should be used.
It is recommended that aggressive chemical dermabrasion and cutaneous laser treatment be avoided in patients on CLARUS® and for a period of 5-6 months after the end of treatment because of the risk of hypertrophic scarring in atypical areas, and more rarely hyper- or hypopigmentation in treated areas.
It is recommended that wax epilation be avoided in patients on CLARUS® therapy and for a period of 5-6 months after treatment because of the risk of epidermal stripping, scarring or dermatitis.
Concurrent administration of CLARUS® with keratolytic or exfoliative anti-acne agents should be avoided as local irritation may increase.
Patients should be advised to use a skin-moisturizing ointment or cream and a lip balm from the start of treatment as isotretinoin is likely to cause dryness of the skin and lips.
- Serious Skin Reactions:
There have been very rare post-marketing reports of severe skin reactions (e.g., erythema multiforme (EM), Stevens-Johnson syndrome (SJS), and toxic epidermal necrolysis (TEN)) associated with isotretinoin use. These events may be serious and result in hospitalization, life threatening events, disfiguration, disability and/or death. Isotretinoin treatment should be discontinued if the patient develops any of the following reactions: rash, especially if associated with fever and/or malaise, conjunctivitis (red or inflamed eyes); blisters on legs, arms or face and/or sores in mouth, throat, nose or eyes; peeling skin or other serious skin reactions.
7.1 Special Populations
7.1.1 Pregnant Women
There is an extremely high risk (25% or greater) that major human fetal abnormalities will occur if pregnancy occurs during treatment with isotretinoin or up to one month following its discontinuation. Potentially any exposed fetus can be affected. These abnormalities, associated with isotretinoin administration during pregnancy, have been reported and include: CNS (hydrocephalus, hydranencephaly, microcephaly, posterior fossa abnormalities, cranial nerve dysfunction, cerebellar malformation); craniofacial (anotia, microtia, low set ears, small or absent external auditory canals, microphthalmia, facial dysmorphia, cleft palate); cardiac (septal defects, aortic arch abnormalities, tetralogy of Fallot); thymus gland abnormalities; and parathyroid hormone deficiency. Cases of IQ scores less than 85 with or without other abnormalities have been reported.
Pregnancy Tests
Female patients of childbearing potential must not be given CLARUS® until pregnancy is excluded. The patient must have two negative pregnancy tests before starting CLARUS® therapy with the first pregnancy test conducted at initial assessment when the patient is qualified for CLARUS® therapy by the physician. A second pregnancy test must be performed within 11 days prior to starting CLARUS® treatment. CLARUS® treatment should start on the second or third day of the next normal menstrual period following this negative pregnancy test.
It is mandatory that all female patients of childbearing potential treated with CLARUS® have regular monthly pregnancy tests during treatment and one month after the discontinuation of treatment. The dates and results of pregnancy tests should be documented. The blood monitoring chart can be used to document these results as well as to serve as a reminder of all the tests that should be carried out and their frequency. This physician material can be downloaded from the www.clarusclearprogram.ca website or by contacting Mylan Pharmaceuticals ULC Customer Service line at 1-844-596-9526.
These pregnancy tests will:
- a) Serve primarily to reinforce to the patient the necessity of avoiding pregnancy.
- b) In the event of accidental pregnancy, provide the physician and patient an immediate opportunity to discuss the serious risk to the fetus from this exposure to CLARUS® and the desirability of continuing the pregnancy in view of the potential teratogenic effect of CLARUS® (see 2 CONTRAINDICATIONS and 16 NON-CLINICAL TOXICOLOGY, Reproduction and Teratology Studies).
7.1.2 Breast-feeding
It is not known whether isotretinoin is excreted in human milk. As isotretinoin is highly lipophilic, the passage of the drug in human milk is very likely. Because of the potential for adverse effects, women should not breast-feed if they are receiving CLARUS® (see 2 CONTRAINDICATIONS).
7.1.3 Pediatrics
<12 years of age: The long term safety of isotretinoin, in prepubertal children, has not been established. No data are available to Health Canada; therefore, Health Canada has not authorized an indication for pediatric use in patients less than 12 years of age.
12 to 17 years of age: In studies with isotretinoin, adverse reactions reported in pediatric patients ages 12 to 17 years were similar to those described in adults except for the increased incidence of back pain and arthralgia (both of which were sometimes severe) and myalgia in pediatric patients (see 8.2 Clinical Trial Adverse Reactions, Musculoskeletal).
Pediatric patients and their caregivers should be informed that approximately 29% (104/358) of pediatric patients treated with isotretinoin developed back pain. Back pain was severe in 13.5% (14/104) of the cases and occurred at a higher frequency in female patients than male patients. Arthralgias were experienced in 22% (79/358) of pediatric patients. Arthralgias were severe in 7.6% (6/79) of patients. Appropriate evaluation of the musculoskeletal system should be done in patients who present with these symptoms during or after a course of CLARUS®. Consideration should be given to discontinuation of CLARUS® if any significant abnormality is found.
7.1.4 Geriatrics
>65 years of age: Clinical studies of isotretinoin did not include sufficient numbers of subjects aged 65 years and over to determine whether they respond differently from younger subjects.
8 ADVERSE REACTIONS
8.1 Adverse Reaction Overview
The adverse reactions listed below reflect the experience from clinical studies of isotretinoin and the post-marketing experience. The relationship of some of these events to isotretinoin therapy is unknown.
Many of the side effects and adverse reactions seen or expected in patients receiving isotretinoin are similar to those described in patients taking high doses of vitamin A.
Adverse reactions were generally reversible when therapy was discontinued; however, some have persisted after cessation of therapy.
8.2 Clinical Trial Adverse Reactions
Dose-Relationship and Duration:
Cheilitis and hypertriglyceridemia are usually dose related.
The most common side effects are mucocutaneous or dermatologic.
The common side effects include: cheilitis (96%), facial erythema/dermatitis (55%), dry nose (51%), desquamation (50%), pruritus (30%), dry skin (22%), conjunctivitis (19%), alopecia (13%), irritation of the eyes (11%), rash (<10%). Dryness of the nasal mucosa and pharynx may be associated with mild epistaxis and hoarseness, respectively. Mild-to-moderate conjunctivitis may be alleviated by use of an ophthalmic ointment. In rare cases, hair loss persisted after treatment was completed.
Approximately 13% of patients experience joint pain during treatment.
Peeling of palms and soles, skin infections, increased susceptibility to sunburn, non-specific urogenital symptoms, non-specific gastrointestinal symptoms, headache, fatigue occurred in approximately 5% of patients.
Body as a whole: weight loss, anemia, lymphadenopathy, vasculitis including Wegener’s granulomatosis, allergic vasculitis, allergic responses, and systemic hypersensitivity.
Cardiovascular: edema, transient pain in the chest, palpitations, tachycardia, vascular thrombotic disease, stroke (see 7 WARNINGS AND PRECAUTIONS, Cardiovascular).
Endocrine and Metabolism: new cases of diabetes (see 7 WARNINGS AND PRECAUTIONS, Endocrine and Metabolism)
Gastrointestinal: nausea, severe diarrhea, mild gastrointestinal bleeding, rectal bleeding, abdominal pain, inflammatory bowel disease (including regional ileitis, colitis and hemorrhage) (see 7 WARNINGS AND PRECAUTIONS, Gastrointestinal).
Hearing Disorders: tinnitus, impaired hearing at certain frequencies.
Hepatic/Biliary/Pancreatic: Patients treated with isotretinoin especially those with high triglyceride levels are at risk of developing pancreatitis. Rare cases of fatal pancreatitis and several cases of clinical hepatitis have been reported (see 7 WARNINGS AND PRECAUTIONS, Hepatic/Biliary/Pancreatic).
Mucocutaneous and Dermatologic: flushing, changes in skin pigment, urticaria, bruising, disseminated herpes simplex, hair problems (other than thinning), hirsutism, erythema nodosum, paronychia, nail dystrophy, pyogenic granuloma, bleeding and inflammation of the gums, acne fulminans, exanthema, sweating, increased formation of granulation tissue, photoallergic/photosensitizing reactions, skin fragility. Acne flare occurs at the start of treatment and persists for several weeks (see 8.5 Post-Market Adverse Reactions).
Musculoskeletal: arthritis, muscle pain (myalgia; elevations of serum CPK values), arthralgia, calcification of ligaments, tendon and tendinitis, reduced bone density, back pain, premature fusion of epiphyses, hyperostosis (see 7 WARNINGS AND PRECAUTIONS, Musculoskeletal, Hyperostosis and 8.5 Post-Market Adverse Reactions).
Neurologic: seizures, dizziness, nervousness, drowsiness, malaise, weakness, insomnia, lethargy, paresthesia, benign intracranial hypertension (see 3 SERIOUS WARNINGS AND PRECAUTIONS BOX, Neurologic).
Ophthalmologic: optic neuritis, photophobia, eye lid inflammation, lenticular cataracts, keratitis, blurred vision, blepharitis, conjunctivitis, decreased night vision, papilledema as sign of benign intracranial hypertension and colour vision disturbances. Dry eyes and/or decreased tolerance to contact lenses have also been reported during therapy. In some instances, these conditions have persisted after cessation of therapy.
Of 72 patients who had normal pre-treatment ophthalmological examinations, five developed corneal opacities while taking isotretinoin (all five patients had a disorder of keratinization). Corneal opacities have also been reported in nodular and/or inflammatory acne patients treated with isotretinoin (see 7 WARNINGS AND PRECAUTIONS, Ophthalmologic). Decrease in night vision has been reported and in rare instances has persisted (see 7 WARNINGS AND PRECAUTIONS, Ophthalmologic). Cataracts and visual disturbances have also been reported.
Psychiatric Disorders: Depression, psychotic symptoms and, rarely, suicide attempts, suicide, and aggressive and/or violent behaviours (see 3 SERIOUS WARNINGS AND PRECAUTIONS BOX, Psychiatric and 7 WARNINGS AND PRECAUTIONS, Psychiatric). Depression has been reported during and after therapy. In some of these patients, depression has subsided with discontinuation of therapy and recurred when isotretinoin therapy was reintroduced. Emotional instability has been reported with isotretinoin.
Respiratory: respiratory infections, bronchospasm has been rarely reported; sometimes in patients with pre-history of asthma.
Reproductive system: abnormal menses, erectile dysfunction.
Urinary system: glomerulonephritis
8.4 Abnormal Laboratory Findings: Hematologic, Clinical Chemistry, and Other Quantitative Data
Isotretinoin therapy induces changes in serum lipids in a significant number of treated subjects. These changes consisted of: elevation of serum triglycerides (25% of patients), mild to moderate decrease in serum high density lipoprotein (HDL) (16% of patients), and minimal elevations of serum cholesterol (7% of patients). Abnormalities of serum triglycerides, HDL and cholesterol were reversible upon cessation of isotretinoin therapy.
A rise in serum levels of liver enzymes may occur, especially with higher dosages. Although the changes have usually been within the normal range, and may return to baseline levels despite continued treatment, significant increases have occurred in a few cases, necessitating dosage reduction or discontinuation of isotretinoin (see 7 WARNINGS AND PRECAUTIONS, Hepatic/Biliary/Pancreatic). An elevated erythrocyte sedimentation rate may also occur (40% of patients).
Other less commonly reported laboratory abnormalities were: Elevated fasting blood sugar, elevated CPK, and hyperuricemia. Decreases in red blood cell parameters, decreases in white blood cell counts, elevated sedimentation rates, elevated platelet counts, thrombocytopenia and anemia. White blood cells in the urine, proteinuria, and red blood cells in the urine.
8.5 Post-Market Adverse Reactions
Mucocutaneous and Dermatologic: During the post-marketing period, Erythema Multiforme (EM), Stevens-Johnson Syndrome (SJS), and Toxic Epidermal Necrolysis (TEN) have been reported to be associated with isotretinoin (see 7 WARNINGS AND PRECAUTIONS, Skin).
Musculoskeletal: There have been post-marketing serious reports of rhabdomyolysis, often leading to hospitalization and some with fatal outcome, particularly in those undergoing strenuous physical activity.
Reproductive system: Sexual dysfunction.
9 DRUG INTERACTIONS
9.2 Drug Interactions Overview
Not applicable.
9.3 Drug-Behavioural Interactions
The interactions of isotretinoin with individual behavioural risks (e.g. cigarette smoking, cannabis use, and/or alcohol consumption) has not been studied.
9.4 Drug-Drug Interactions
Tetracyclines: Rare cases of benign intracranial hypertension ‘pseudotumor cerebri’ have been reported after use of isotretinoin and/or tetracyclines. Therefore, concomitant treatment with tetracyclines must be avoided (see 3 SERIOUS WARNINGS AND PRECAUTIONS BOX, Neurologic).
Vitamin A: Because of the relationship of isotretinoin to vitamin A, patients should be advised against taking vitamin supplements containing vitamin A, to avoid additive toxic effects.
Phenytoin: Isotretinoin has not been shown to alter the pharmacokinetics of phenytoin in a study in seven healthy volunteers. These results are consistent with the in vitro finding that neither isotretinoin nor its metabolites induce or inhibit the activity of the CYP 2C9 human hepatic P450 enzyme. Phenytoin is known to cause osteomalacia. No formal clinical studies have been conducted to assess if there is an interactive effect on bone loss between phenytoin and isotretinoin. Therefore, caution should be exercised when using these drugs together.
Norethindrone/ethinyl estradiol: In a study of 31 premenopausal women with severe recalcitrant nodular acne receiving OrthoNovum® 7/7/71 Tablets as an oral contraceptive agent, isotretinoin at the recommended dose of 1 mg/kg/day, did not induce clinically relevant changes in the pharmacokinetics of ethinyl estradiol and norethindrone and in the serum levels of progesterone, follicle-stimulating hormone (FSH) and luteinizing hormone (LH). A drug interaction that decreases effectiveness of hormonal contraceptives has not been entirely ruled out for isotretinoin.
Microdosed progesterone preparations (minipills) are not a suitable method of contraception during CLARUS® therapy.
Systemic Corticosteroids: Systemic corticosteroids are known to cause osteoporosis. No formal clinical studies have been conducted to assess if there is an interactive effect on bone loss between systemic corticosteroids and isotretinoin. Therefore, caution should be exercised when using these drugs together.
9.5 Drug-Food Interactions
Due to its lipophilic properties, absorption of isotretinoin is increased when taken with food. Therefore, the recommended dose is to be taken with food (see 4.2 Recommended Dose and Dosage Adjustment).
9.6 Drug-Herb Interactions
St. John’s Wort: Isotretinoin use is associated with depression in some patients (see 3 SERIOUS WARNINGS AND PRECAUTIONS BOX, Psychiatric). Patients should be prospectively cautioned not to self-medicate with the herbal supplement St. John’s Wort because a possible interaction has been suggested with hormonal contraceptives based on reports of breakthrough bleeding on oral contraceptives shortly after starting St. John’s Wort. Pregnancies have been reported by users of combined hormonal contraceptives who also used some form of St. John’s Wort.
1 Ortho-Novuum® 7/7/7 is a registered Trade-Mark of Johnson & Johnson
9.7 Drug-Laboratory Test Interactions
See 8.4 Abnormal Laboratory Findings: Hematologic, Clinical Chemistry, and Other Quantitative Data.
10 ACTION AND CLINICAL PHARMACOLOGY
10.1 Mechanism of Action
The mechanism of action of isotretinoin is unknown. Vitamin A is important for functional integrity of the skin and is known to affect the keratinization process. In acne patients, improvement occurs in association with a reduction in sebum secretion. The decrease in sebum secretion is temporary and is related to either the dose or duration of isotretinoin administration and reflects a reduction in sebaceous gland size and an inhibition of sebaceous gland differentiation.
10.2 Pharmacodynamics
Isotretinoin exerts a specific action on the sebaceous glands of the hamster flank organs. Subcutaneous administration of isotretinoin to female hamsters treated simultaneously with testosterone enanthate prevents the androgen induced growth of flank organ sebaceous glands without affecting other androgen dependent cells (i.e. does not inhibit development of pigment or larger hair follicles).
Doses up to 300 mg/kg orally of isotretinoin have no effect upon circulation and respiratory parameters in the anesthetized cat. A dose of 1 g/kg results in respiratory stimulation and a slight decrease in blood pressure, pulse rate, blood flow to the extremities as well as oxygen saturation.
10.3 Pharmacokinetics
Absorption: Following oral administration of 80 mg, peak plasma concentrations ranged from 167 to 459 ng/mL (mean 256 ng/mL) with a mean time to peak of 3.2 hours in volunteers, while in acne patients peak plasma concentrations ranged from 98 to 535 ng/mL (mean 262 ng/mL) with a mean time to peak of 2.9 hours.
When isotretinoin is taken with food, the bioavailability is doubled relative to fasting conditions (see 4 DOSAGE AND ADMINISTRATION).
Distribution: Isotretinoin is 99.9% protein bound in human plasma, almost exclusively to albumin.
Metabolism: The major metabolite identified in blood and urine was 4-oxo-isotretinoin. Tretinoin and 4-oxo-tretinoin were also observed. The apparent half-life for elimination of the 4-oxo-isotretinoin ranged from 11 to 50 hours, with a mean of 28 hours. Following 80 mg of isotretinoin administered orally, maximum plasma concentrations of the 4-oxo-isotretinoin was 87 to 399 ng/mL and maxima were observed between 6 and 20 hours. The blood concentration of the major metabolite generally exceeded that of isotretinoin after 6 hours. The data suggest that both isotretinoin and the major metabolite are excreted in the bile and reabsorbed.
The mean minimum steady-state blood concentrations of isotretinoin were 160 ng/mL in 10 patients receiving 40 mg twice daily doses. After single and multiple doses, the mean ratio of areas under the curves of 4-oxo-isotretinoin to isotretinoin was between 3 and 3.5.
Elimination: The mean terminal elimination half-life of isotretinoin in patients with acne has a mean value of 19 hours. Following oral administration of 14C-isotretinoin, 14C activity in blood declined with a mean half-life of 90 hours. Approximately equal amounts of radioactivity were recovered in the urine and feces, with 65-83% of the dose recovered.
Special Populations and Conditions
Pediatrics: The pharmacokinetics of isotretinoin were evaluated after single and multiple doses in 38 pediatric patients (12 to 15 years) and 19 adult patients (≥18 years) who received isotretinoin for the treatment of severe recalcitrant nodular acne. In both age groups, 4-oxo-isotretinoin was the major metabolite; tretinoin and 4-oxo-tretinoin were also observed. The dose-normalized pharmacokinetic parameters for isotretinoin following single and multiple doses are summarized in Table 2 for pediatric patients. There were no statistically significant differences in the pharmacokinetics of isotretinoin between pediatric and adult patients.
Table 2 - Pharmacokinetic Parameters of Isotretinoin Following Single and Multiple Dose Administration in Pediatric Patients, 12 to 15 Years of Age Mean (± SD), N=38*
| Cmax (ng/mL) | Tmax (hr)† | T1/2 (hr) | AUC(0-12) (ngxhr/mL) | AUC(0-24) (ngxhr/mL) | CL/F (L/hr) | CSSmin (ng/mL) | |
|---|---|---|---|---|---|---|---|
| Single Dose | 573.25 (278.79) | 6.00 (1.00-24.60) | - | 3033.37 (1394.17) | 6003.81 (2885.67) | - | - |
| Steady-State | 731.98 (361.86) | 4.00 (0-12.00) | 15.69 (5.12) | 5082.00 (2184.23) | - | 17.96 (6.27) | 352.32 (184.44) |
* The single and multiple dose data in this table were obtained following a non-standardized meal (non-high-fat meal).
† Median (range)
In pediatric patients (12 to 15 years), the mean ± SD elimination half-lives (t1/2) of isotretinoin and 4-oxo-isotretinoin were 15.7 ± 5.1 hours and 23.1 ± 5.7 hours, respectively. The accumulation ratios of isotretinoin ranged from 0.46 to 3.65 for pediatric patients.
Overdosage: Following the oral administration of single 80, 160, 240 and 340 mg doses to 12 healthy male subjects Cmax was 366, 820, 1,056 and 981 ng/mL, and t1/2 was 13.6, 14.1, 14.4 and 16.5 hours for isotretinoin, respectively. Twenty-three compromised cancer patients received weekly oral doses of 200 (3 patients); 400 (7 patients); 660 (2 patients); 1,000 (3 patients); 1,400 (6 patients) and 1,800 (1 patient) mg/m2. Normal body surface area for healthy subjects is 1.73 m2. After the first dose, Cmax was 1.5, 3.8, 3.5, 2.5, 2.7 and 4.6 μg/mL, and t1/2 was 45, 9.1, 14.5, 57, 13.1 and 6.1 hours for isotretinoin, respectively. The absorption of isotretinoin appears to be a saturable process.
11 STORAGE, STABILITY AND DISPOSAL
CLARUS® (isotretinoin) 10 mg and 40 mg capsules: Store at controlled room temperature (15°C to 30°C). Store in the original package. Protect from exposure to heat and light.
Keep in a safe place out of the reach of children.
CLARUS® meets USP Dissolution Test 3.
12 SPECIAL HANDLING INSTRUCTIONS
The release of pharmaceuticals in the environment should be minimized. Medicines should not be disposed of via wastewater and disposal through household waste should be avoided. Use established “collection systems” if available in your location.
Return any unused CLARUS® (isotretinoin) capsules to the pharmacist.
PART II: SCIENTIFIC INFORMATION
13 PHARMACEUTICAL INFORMATION
Drug Substance
Proper Name: Isotretinoin
Chemical Name: 3-7-dimethyl-9-(2,6,6-trimethyl-1-cyclo-hexen-1-yl)-2,4,6,8- nonatetraenoic acid
Molecular Formula: C20H28O2
Molecular Weight: 300.44 g/mol
Structural Formula:
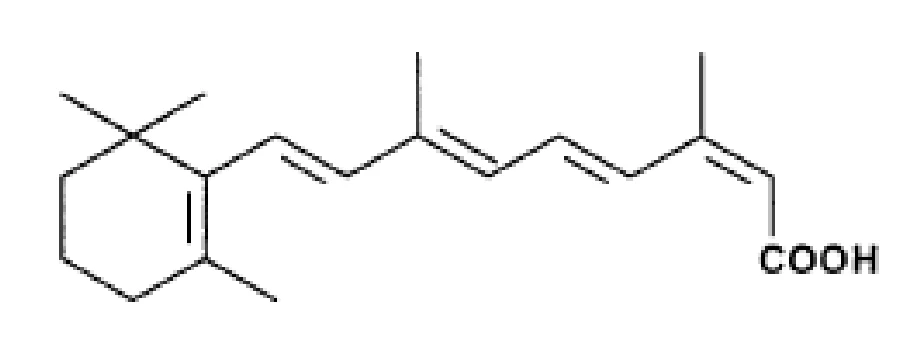
Physiochemical properties:
Pharmaceutical standard:
Orange crystalline powder, insoluble in water; soluble in chloroform (10g / 100 mL). Melting point approximately 175°C; pKa approximately 4.
USP
14 CLINICAL TRIALS
Clinical trials were not labeled at the time of authorization; therefore, no clinical trial data are available.
14.2 Comparative Bioavailability Studies
A blinded, randomized, single-dose, 2-way crossover, relative bioavailability study was conducted in healthy volunteers to compare CLARUS® 40 mg soft gelatin capsules and AccutaneTM 40 mg soft gelatin capsules under fed conditions. The pharmacokinetic data is summarized below.
Summary Table of the Comparative Bioavailability Data for Single Dose Fed Study
Isotretinoin (2 x 40 mg) From measured data Geometric Mean Arithmetic Mean (CV%) | ||||
| Parameter | Test* | Reference† | % Ratio of Geometric Means | 95% Confidence Interval |
| AUCT (ng.h/ml) | 10228.66 10397.5 (18.0%) | 11257.18 11455.8(18.5%) | 90.9% | 87.3%-94.6% |
AUCINF (ng.h/ml) | 10591.93 10772.1 (18.2%) | 11647.46 11856.6 (18.7%) | 90.9% | 87.4%-94.6% |
CMAX (ng/ml) | 1134.17 1221.5 (36.5%) | 1260.06 1374.81 (38.6%) | 90.0% | 81.7%-99.2% |
TMAX * (h) | 4.406 (36.8%) | 5.129 (60.1%) | ||
T1/2 * (h) | 15.75 (16.9%) | 15.55 (18.7%) | ||
*CLARUS® soft gelatine capsules manufactured by Mylan Pharmaceuticals ULC, Etobicoke, Canada
† AccutaneTM soft gelatin capsules manufactured by Hoffmann-LaRoche Limited/ Limitée (Canada) were purchased in Canada.
* Expressed as arithmetic mean (CV%) only.
A blinded, randomized, single-dose, 2-way crossover, relative bioavailability study was conducted in healthy volunteers to compare CLARUS 40 mg soft gelatin capsules and AccutaneTM 40 mg soft gelatin capsules under fasting conditions. The pharmacokinetic data is summarized below.
Summary Table of the Comparative Bioavailability Data for Single Dose Fasted Study
Isotretinoin (2 x 40 mg) From measured data Geometric Mean Arithmetic Mean (CV%) | ||||
| Parameter | Test* | Reference† | % Ratio of Geometric Means | 95% Confidence Interval |
| AUCT (ng.h/ml) | 4247.97 4481.4 (33.7%) | 4412.22 4636.2 (3 1.2%) | 96.3% | 86.3%-107.5% |
AUCINF (ng.h/ml) | 4567.88 4812.5 (33.2%) | 4819.48 5037.7 (30.2%) | 94.8% | 85.5%-105.1% |
CMAX (ng/ml) | 390.98 407.35 (27.4%) | 386.46 407.63 (32.4%) | 101.2% | 90.6%-113.0% |
TMAX * (h) | 3.892 (103.0%) | 3.208 (51.8%) | ||
T1/2 * (h) | 20.06 (21.3%) | 20.76 (40.9%) | ||
*CLARUS® soft gelatine capsules manufactured by Mylan Pharmaceuticals ULC, Etobicoke, Canada
† AccutaneTM soft gelatin capsules manufactured by Hoffmann-LaRoche Limited/ Limitée (Canada) were purchased in Canada.
* Expressed as arithmetic mean (CV%) only.
15 MICROBIOLOGY
Not applicable.
16 NON-CLINICAL TOXICOLOGY
General Toxicology
Acute Toxicity Studies
| Animal | Route | LD50 | Observation Period |
| mouse | oral | 3,389 mg/kg | -- |
| mouse | intraperitoneal | 904 mg/kg | 10, 20 days |
| rat | oral | > 4,000 mg/kg | 14 days |
| rat | intraperitoneal | 901 mg/kg | 10, 20 days |
| rabbit | oral | approx. 1,960 mg/kg | 14 days |
(Signs and symptoms: sedation and respiratory depression)
Pyramiding doses of 4.8, 13.1, 41.2 and 79.8 mg/kg of isotretinoin were administered to dogs. All dogs survived. Diarrhea occurred in dogs treated with doses of 13.1 mg/kg or higher.
Long-Term Toxicity Studies
55-week Oral Toxicity - Dog
In a 55-week toxicity study conducted in beagle dogs (9/sex/group), isotretinoin was administered as a dietary admix at doses of 3, 20 or 120 mg/kg/day. Severe toxicity developed in the high-dose group and administration was stopped at the end of week 4. Isotretinoin was restarted in this group at the end of 12 weeks, but at a reduced dosage of 60 mg/kg/day. After 7 weeks, administration again had to be stopped for 6 weeks. Administration continued uninterrupted until week 30. Thereafter, the high-dose group was maintained on a cycle of 2 weeks no treatment followed by 6 weeks of treatment with 60 mg/kg/day.
In the high-dose group (60/120 mg/kg/day), the following toxic manifestations were observed: weight loss, skin lesions, visible blood in feces, ophthalmological changes (epiphora, superficial punctate corneal opacities in the subepithelial stroma, vascularization of the subepithelial corneal stroma and congestion or hyperemia of the palpebral and/or bulbar conjunctiva), decreases in hematocrit and hemoglobin, decreased mean serum glucose levels, slight alterations in mean serum transaminase activity, elevations in mean serum alkaline phosphatase activity, and qualitative albuminuria.
Most clinical signs of toxicity disappeared or diminished when isotretinoin was withdrawn and reappeared when treatment was reactivated. Pathological changes in the high-dose group included: increased incidence of focal gross lesions in the gastrointestinal tract, testicular atrophy with evidence of spermatogenic arrest, increased mean liver weight, microscopic evidence for edema and/or erythrophago-cytosis of the lymph nodes, encephalomalacia limited to single microscopic foci in the brain of two dogs, and degeneration of elastic fibre in four dogs.
Many of the clinical and pathological signs, except for weight loss and corneal opacities, seen in the high dosage group were also evident in the dogs treated with 20 mg/kg/day. However, a tendency towards a decreased frequency and a longer time to first appearance than in the high-dose group was noted.
The low dosage (3 mg/kg/day) was well tolerated, but microscopic changes in the lymph nodes were observed in the same number of dogs as was recorded for the mid-dose group.
Two-year Oral Toxicity - Rat
Isotretinoin was administered to rats (80/sex/group) as a dietary admix for two years. All groups received 1 mg/kg/day for 13 weeks in order to avoid excessive bone fractures during the major period of growth. Thereafter, doses of 2, 8 and 32 mg/kg/day were administered. In the high-dose group, administration of drug was discontinued during weeks 29-41 and 67-73 due to long bone fracture.
All observed side effects of hypervitaminosis A syndrome were spontaneously reversible after withdrawal of isotretinoin. Even experimental animals in a poor general state had largely recovered within 1-2 weeks.
32 mg/kg/day
Upon completion of the study, the following clinical and laboratory findings were observed in the high dose group: increased mortality, decreased body weight gain and food consumption; altered gait (related to possible long bone fracture); decreased hemoglobin and hematocrit; elevated serum alkaline phosphatase, serum triglycerides, serum phosphate, and serum urea nitrogen; exacerbated age- and sialodacryoadenitis (SDA) virus-related eye changes; skin lesions; some increased organ weights. The following histopathological findings were noted: reduplication of small bile ducts; focal fibrosis and focal chronic inflammation of the heart; focal dilation of renal tubules and focal chronic inflammation of the kidney; adrenal medullary lesions (hyperplasia and pheochromocytomas); arteritis; calcification of arteries; focal calcification in tissues; focal osteolysis of bone.
8 mg/kg/day
When isotretinoin was administered to rats at 8 mg/kg/day as a dietary admix for two years, the clinical and laboratory findings were: increased mortality; decreased body weight gain; decreased hemoglobin and hematocrit; elevated serum alkaline phosphatase and serum triglycerides; exacerbated age- and SDA virus-related eye changes; skin lesions; some increased organ weights. The histopathological findings were: reduplication of small bile ducts; focal fibrosis and focal chronic inflammation in the heart; renal tubular dilation and focal chronic inflammation in the kidney; adrenal medullary lesions (hyperplasia and pheochromocytomas); arteritis; calcification of arteries; focal calcification in tissues; focal osteolysis of bone.
2 mg/kg/day
When isotretinoin was administered to rats at 2 mg/kg/day as a dietary admix for two years, the clinical and laboratory findings were: elevated serum alkaline phosphatase values, some increased organ weights. The histopathological findings were: reduplication of small bile ducts; increased focal chronic inflammation of the kidneys; arteritis; calcification of arteries; focal calcification in tissues.
Although an increased incidence of pheochromocytomas and adrenal medullary hyperplasia were observed at the high and mid doses, no increase was observed at the low dose. It is very likely that this increase in number of adrenal medullary proliferative lesions was mediated by an effect upon hormonal status in rats that were already hormonally abnormal because of their genetic origin and overfeeding, as well as other aspects of the environment of laboratory rats. Dose-related decreases in the incidence of liver adenomas and angiomas in male rats and leukemia in female rats were also noted.
Genotoxicity
Mutagenicity Testing
Isotretinoin was non-mutagenic in the Ames Test at concentrations up to 2 mg per plate in the absence or presence of metabolic activation.
Carcinogenicity
Isotretinoin has not been shown to be mutagenic or carcinogenic in in vitro or in vivo animal tests, respectively.
Reproductive and Developmental Toxicology
Like other Vitamin A derivatives, isotretinoin has been shown in animal experiments to be teratogenic and embryotoxic; however, there is a large species variation in the teratogenic effect. Rats have been reported to be less sensitive to the teratogenic effects of isotretinoin; whereas, humans have been reported to be the most sensitive. Differences in sensitivity are a result of interspecies differences in the pharmacokinetics and placental transfer of isotretinoin.
The following table provides the low dose (mg/kg) reported to elicit teratogenesis in animal models.
| Species | Low dose to elicit teratogenic effect |
| Mouse/rat | 75-150 mg/kg |
| Rabbit | 10 mg/kg |
| Monkey | 2.5-5 mg/kg |
| Human | 0.4-1 mg/kg |
Fertility and General Reproductive Performance - Rat
Isotretinoin at doses of 2, 8 or 32 mg/kg/day was administered orally to male rats for 63 days prior to mating and through the mating period and to females for 14 days prior to mating and through day 13 of gestation or day 21 of gestation or day 21 of lactation. No adverse effects on fertility and general reproductive performance were observed except for a slight reduction in the weight of weanlings in the high-dose group.
Teratology - Rat
A teratology study was conducted in rats with 5, 15 or 50 mg/kg/day of isotretinoin administered orally on gestation days 7 through 15. Doses of up to 50 mg/kg/day of isotretinoin were found to be non-teratogenic. In an earlier study a dose of 150 mg/kg/day was observed to be teratogenic.
Teratology - Rabbit
New Zealand white rabbits were administered isotretinoin at doses of 1, 3 or 10 mg/kg/day on days 7 through 18 of gestation. No teratogenic or embryotoxic effects were observed at 1 and 3 mg/kg/day. At 10 mg/kg/day, 9/13 does aborted and teratogenicity and embryotoxicity were observed in the remaining four litters.
Perinatal and Postnatal Evaluation - Rat
Rats were administered isotretinoin at doses of 5, 15 or 32 mg/kg/day orally from gestation day 14 through day 21 of lactation. Increased pup mortality, considered secondary to reduced maternal food intake, was noted in all treated groups and particularly in the high-dose group. Body weight development of pups was impaired significantly in the high-dose group. Similarly, this effect was considered due to a reduced food intake by the dams.
17 SUPPORTING PRODUCT MONOGRAPHS
PrACCUTANE™ Capsule, 10 mg, 40 mg, control 296674, product monograph, CHEPLAPHARM Schweiz GmbH. (2025-09-05)