


Product Monograph - Coated Daily Low Dose ASA 81 mg
1 INDICATIONS
COATED DAILY LOW DOSE ASA 81 mg (acetylsalicylic acid, ASA) is indicated for the following uses, based on its platelet aggregation inhibitory properties:
- for reducing the risk of vascular mortality in patients with a suspected acute myocardial infarction;
for reducing the risk of a first non-fatal myocardial infarction in individuals deemed to be at sufficient risk of such an event by their physician.
- There is no evidence for a reduction in the risk of first fatal myocardial infarction.
- COATED DAILY LOW DOSE ASA 81 mg does not reduce the risk of either cardiovascular mortality or first strokes, fatal or non-fatal.
- The decrease in the risk of first non-fatal myocardial infarction must be assessed against a much smaller but not insignificant increase in the risk of haemorrhagic stroke as well as gastrointestinal bleeding.
- for reducing the risk of morbidity and death in patients with unstable angina and in those with previous myocardial infarction
- for reducing the risk of transient ischemic attacks (TIA) and for secondary prevention of atherothrombotic cerebral infarction;
- for prophylaxis of venous thromboembolism after total hip replacement;
1.1 Pediatrics
Pediatrics (under 12): Based on the data submitted and reviewed by Health Canada for certain uses (See 4.2 Recommended Dose and Dosage Adjustment), the safety and efficacy of acetylsalicylic acid in pediatric patients has been established. However, a possible association between Reye's syndrome and the use of salicylates has been suggested but not established. ASA should not be used in children and teenagers for viral infections with or without fever without consulting a physician. (See 7 WARNINGS AND PRECAUTIONS).
1.2 Geriatrics
Geriatrics: Evidence from clinical studies and experience suggests that use in the geriatric population is associated with differences in safety or effectiveness. (See 7 WARNINGS AND PRECAUTIONS) In general, ASA should be used with caution in elderly patients (≥ 60 years of age), as these patients may be more susceptible to adverse reactions.
2 CONTRAINDICATIONS
COATED DAILY LOW DOSE ASA 81 mg is contraindicated in patients who are/have:
- Hypersensitive to ASA, salicylates, non-steroidal anti-inflammatory drugs (NSAIDs), analgesics, antipyretics or other ingredients in the product or component of the container. For a complete listing, see 6 DOSAGE FORMS, STRENGTHS, COMPOSITION AND PACKAGING of the product monograph.
- Acute gastrointestinal ulcer
- History of gastrointestinal ulcers
- Hemorrhagic diathesis
- Active or Severe hepatic failure, renal failure, or congestive heart failure
- History of asthma induced by the administration of salicylates or substances with a similar action, notably NSAIDs
- Concomitant treatment with methotrexate at doses of 15mg/week or more (see 9 DRUG INTERACTIONS).
- The third trimester of pregnancy, because of risk of premature closure of the ductus arteriosus, and prolonged parturition. (see 7.1 Special Populations)
3 SERIOUS WARNINGS AND PRECAUTIONS BOX
| Risk in Pregnancy: Caution should be exercised in prescribing COATED DAILY LOW DOSE ASA 81 mg during the first and second trimesters of pregnancy. Use of NSAIDS at approximately 20 weeks of gestation or later may cause oligohydramnios, and renal dysfunction including renal failure (see 7 WARNINGS AND PRECAUTIONS). COATED DAILY LOW DOSE ASA 81 mg is CONTRAINDICATED for use during the third trimester because of risk of premature closure of the ductus arteriosus and uterine inertia (prolonged parturition) (see 2 CONTRAINDICATIONS). |
|---|
4 DOSAGE AND ADMINISTRATION
4.1 Dosing Considerations
- Please see below for specific dosing instructions for each indication.
4.2 Recommended Dose and Dosage Adjustment
Platelet aggregation inhibitor:
Suspected Acute Myocardial Infarction:
An initial dose of at least 162 mg chewed to ensure rapid absorption as soon as a myocardial infarction is suspected. The same dose should be given as maintenance over the next 30 days. After 30 days, consider further therapy based on dosage and administration for prevention of recurrent MI (see Prior Myocardial Infarction).
Prevention of a first non-fatal myocardial infarction:
81 to 325 mg once daily, according to the individual needs of the patient, as determined by the physician.
Prior Myocardial Infarction or Unstable Angina Pectoris:
81 to 325 mg daily according to the individual needs of the patient, as determined by the physician.
Transient Ischemic Attack and Secondary Prevention of Atherothrombotic Cerebral Infarction:
81 to 325 mg daily according to the individual needs of the patient, as determined by the physician.
Prophylaxis of Venous Thromboembolism after total hip replacement:
162 to 325 mg daily according to the individual needs of the patient, as determined by the physician.
4.4 Administration
ASA tablets should preferably be taken after meals, with plenty of liquid.
4.5 Missed dose
Take the missed dose as soon as you remember. But do not take an extra dose to compensate for a missed dosage unless instructed by your doctor.
5 OVERDOSAGE
Mild Overdose or Early Poisoning - burning in the mouth, lethargy, nausea, vomiting, tinnitus, sweating, thirst, tachycardia or dizziness.
Moderate Overdose - all of the symptoms from mild overdose plus tachypnea, hyperpyrexia, sweating, dehydration, loss of coordination, restlessness, mental confusion.
Severe Overdose - all of the symptoms from moderate overdose plus hypotension, hallucinations, stupor, hypoglycemia, convulsions, cerebral edema, oliguria, renal failure, cardiovascular failure, coma, hemorrhage, metabolic acidosis, respiratory alkalosis and/or failure.
Emergency Management:
- 1. Immediate transfer to hospital and maintain cardiovascular and respiratory support.
- 2. Gastric lavage, administration of activated charcoal,
- 3. Check of acid-base balance and correct if necessary.
- 4. Alkaline diuresis so as to obtain urine pH between 7.5 and 8 should be considered when plasma salicylate concentration is greater than 500mg/L (3.6 mmol/L) in adults or 300mg/L (2.2 mmol/L) in children
- 5. Hemodialysis should be considered in severe poisoning 800mg/L (5.8 mmol/L) in adults and 700mg/L (5.0 mmol/L) in children, as renal elimination of salicylates may be slow due to the presence of acidic urine and renal failure. Hemodialysis should also be considered if the patient is experiencing severe systemic metabolic acidosis (arterial pH < 7.2), acute renal failure, pulmonary edema or CNS symptoms such as: drowsiness, agitation, coma or convulsions.
- 6. Fluid losses should be replaced with hypotonic solution (e.g. half saline) and supplemented with glucose 50 to 100g/L.
- 7. Symptomatic treatment.
Fatal Dose: varies from 10 to 30g of ASA. However, (in one case) 130g of ASA was ingested without fatal outcome.
| For management of a suspected drug overdose, contact your regional poison control centre. |
|---|
6 DOSAGE FORMS, STRENGTHS, COMPOSITION AND PACKAGING
Table 1 – Dosage Forms, Strengths, Composition and Packaging
| Route of Administration | Dosage Form / Strength / Composition | Non-medicinal Ingredients |
| Oral | Delayed Release Tablet 81 mg | Corn starch, FD&C Blue # 1, hydroxypropyl methylcellulose, methacrylic acid copolymer, microcrystalline cellulose, polyethylene glycol, talc, titanium dioxide and triethyl citrate. |
Each blue, round enteric-coated tablet, engraved ‘APO’ on one side and ‘81’ on other side, contains 81 mg acetylsalicylic acid.
Available in bottles of 8, 24, 30, 90, 100, 120, 125, 150, 180, 240, 250, 500 and 1000 tablets.
7 WARNINGS AND PRECAUTIONS
General
ASA is one of the most frequent causes of accidental poisonings in toddlers and infants.
Tablets should be kept well out of the reach of children.
ASA should be administered cautiously to patients with:
- Uncontrolled hypertension
- Impaired hepatic, renal function or cardiovascular circulation (e.g., Renal vascular disease, congestive heart failure, volume depletion, major surgery, sepsis or major haemorrhagic events)
- A history of bleeding tendencies, significant anemia and/or hypothrombinemia
- Concomitant treatment with anticoagulants (see 9.4 Drug-Drug Interactions)
- Concomitant treatment with NSAIDs, such as ibuprofen and naproxen in patients on an ASA regimen (see 9.4 Drug-Drug Interactions)
Hematologic
Due to effect on platelet aggregation, ASA may be associated with an increased risk of bleeding. Caution is necessary when salicylates and anticoagulants are prescribed concurrently, as salicylates can depress the concentration of prothrombin in the plasma.
Immune
ASA may precipitate bronchospasm and induce asthma attacks or other hypersensitivity reactions. Risk factors are present bronchial asthma, hay fever, nasal polyps, or chronic respiratory disease. This applies also for patients showing allergic reactions (e.g., cutaneous reactions, itching, urticaria) to other substances.
Monitoring and Laboratory Tests
Salicylates can produce changes in thyroid function tests.
Isolated cases of liver function disturbances (transaminases increase) have been described.
Pregnancy: If COATED DAILY LOW DOSE ASA 81 mg is administered in the middle (approximately 20 weeks) to the end of the second trimester, it is recommended that pregnant women on COATED DAILY LOW DOSE ASA 81 mg be closely monitored for amniotic fluid volume since COATED DAILY LOW DOSE ASA 81 mg may result in reduction of amniotic fluid volume and even oligohydramnios (see 7.1 Special Populations). COATED DAILY LOW DOSE ASA 81 mg is CONTRAINDICATED for use in the third trimester of pregnancy.
Antenatal monitoring for ductus arteriosus constriction should be considered after exposure to acetyl salicylic acid from gestational week 20 onward. Treatment with acetyl salicylic acid should be discontinued if ductus arteriosus constriction is found.
Peri-Operative Considerations
Due to its inhibitory effect on platelet aggregation which persists for several days after administration, ASA may lead to an increased bleeding tendency during and after surgical operations (including minor surgeries, e.g., dental extractions).
Reproductive Health: Female and Male Potential
- Fertility
Based on the limited published data available, the studies in humans showed no consistent effect of acetylsalicylic acid on impairment of fertility and there is no conclusive evidence from animal studies.
7.1 Special Populations
Low Uric Acid Excretion:
At low doses, ASA reduces excretion of uric acid. This can trigger gout in patients who already tend to have low uric acid excretion.
Glucose-6-phosphate dehydrogenase (G6PD) Deficiency:
In patient suffering from glucose-6-phosphate dehydrogenase (G6PD) deficiency, ASA may induce hemolysis or haemolytic anemia. Factors that may increase the risk of haemolysis are high dosage, fever, or acute infections.
7.1.1 Pregnant Women
Women attempting to conceive:
Based on the limited published data available, the studies in humans showed no consistent effect of acetylsalicylic acid on impairment of fertility and there is no conclusive evidence from animal studies.
Pregnant Women:
During the first and second trimester of pregnancy, acetylsalicylic acid containing drugs should not be given unless clearly necessary. If acetylsalicylic acid containing drugs are used by a woman attempting to conceive, or during the first and second trimester of pregnancy, the dose should be kept as low as possible and duration of treatment as short as possible.
Oligohydramnios/Neonatal Renal Impairment:
Use of NSAIDs, including acetylsalicylic acid, at approximately 20 weeks gestation or later in pregnancy may cause fetal renal dysfunction leading to oligohydramnios and, in some more severe cases, neonatal respiratory, musculoskeletal and renal problems.
Published studies and post-marketing reports describe maternal NSAID use at approximately 20 weeks gestation or later in pregnancy associated with fetal renal dysfunction leading to oligohydramnios, and in some cases, neonatal renal impairment, or failure. NSAIDs were shown to cause significant reduction in fetal urine production prior to reduction of amniotic fluid volume. There have also been a limited number of case reports of maternal NSAID use and neonatal renal dysfunction without oligohydramnios, some of which were irreversible, even after treatment discontinuation.
These adverse outcomes are seen, on average, after days to weeks of treatment, although oligohydramnios has been infrequently reported as soon as 48 hours after NSAID initiation. Oligohydramnios is often, but not always, reversible with treatment discontinuation.
Complications of prolonged oligohydramnios may, for example, include limb contractures and delayed lung maturation. In some post-marketing cases of impaired neonatal renal function, invasive procedures such as exchange transfusion or dialysis were required.
If, after careful consideration of alternative treatment options for pain management, NSAID treatment is necessary anywhere from the middle (onset approximately 20 weeks) to the end of the second trimester of pregnancy, it is recommended that the use be limited to the lowest effective dose and shortest duration possible.
Consider ultrasound monitoring of fetal well-being, including of amniotic fluid volume assessment if acetylsalicylic acid treatment extends beyond 48 hours. It is recommended that NSAIDs treatment be discontinued if oligohydramnios occurs, followed by appropriate medical follow up.
Inform pregnant women not to use acetylsalicylic acid and other NSAIDs from the third trimester of pregnancy because of the risk of the premature closing of the fetal ductus arteriosus. If treatment with acetylsalicylic acid is needed for a pregnant woman anywhere from the middle (onset approximately 20 weeks gestation) to the end of the second trimester of pregnancy, advise her that she may need to be monitored for oligohydramnios, if treatment continues for longer than 48 hours.
Also, there have been reports of ductus arteriosus constriction following treatment in the second trimester, most of which resolved after treatment cessation. Antenatal monitoring for ductus arteriosus constriction should be considered after exposure to acetyl salicylic acid from gestational week 20 onward. Treatment with acetyl salicylic acid should be discontinued if ductus arteriosus constriction is found.
Acetylsalicylic acid inhibits prostaglandin synthesis. Inhibition of prostaglandin synthesis may adversely affect the pregnancy and/or the embryo/fetal development. Data from epidemiological studies suggest an increased risk of miscarriage and of cardiac malformation after use of a prostaglandin synthesis inhibitor in early pregnancy. In animals, administration of a prostaglandin synthesis inhibitor has been shown to result in increased pre- and post- implantation loss and embryo-fetal lethality. In addition, increased incidences of various malformations, including cardiovascular, have been reported in animals given a prostaglandin synthesis inhibitor during the organogenetic period. Data from epidemiological studies raise concern about an increased risk of miscarriage and of malformations after the use of a prostaglandin synthesis inhibitor in early pregnancy. The risk is believed to increase with dose and duration of therapy. Available data do not support any association between intake of acetylsalicylic acid and an increased risk for miscarriage. For acetylsalicylic acid the available epidemiological data regarding malformation are not consistent, but an increased risk of gastroschisis could not be excluded. A prospective study with exposure in early pregnancy (1st to 4th month) of about 14,800 mother-child pairs has not yielded any association with an elevated rate of malformations.
- During the third trimester of pregnancy, all prostaglandin synthesis inhibitors may expose the foetus to: Cardiopulmonary toxicity (Constriction/premature closure of the ductus arteriosus and pulmonary hypertension); Renal dysfunction, which may progress to renal failure with oligo-hydroamniosis.
Use of any prostaglandin synthesis inhibitors at the end of pregnancy may expose the mother and the child to:
Possible prolongation of bleeding time, an anti-aggregating effect which may occur even after very low doses;
Inhibition of uterine contractions resulting in delayed or prolonged labour.
Consequently, acetylsalicylic acid is contraindicated in the third trimester of pregnancy.
7.1.2 Breast-feeding
ASA and its metabolites pass into breast milk in small quantities. Since no adverse effects on the infant have been observed after occasional use, interruption of breast-feeding is usually unnecessary. However, on regular use or on intake of high doses, breast feeding should be discontinued early.
7.1.3 Pediatrics
A possible association between Reye's syndrome and the use of salicylates has been suggested but not established. Reye's syndrome has also occurred in many patients not exposed to salicylates. ASA should not be used in children and teenagers for viral infections with or without fever without consulting a physician. In certain viral illnesses, especially influenza A, influenza B and varicella, there is a risk of Reye’s syndrome, a very rare but possibly life-threatening illness requiring immediate medical action. The risk may be increased when ASA is given concomitantly; however, no causal relationship has been proven. Should persistent vomiting occur with such diseases; this may be a sign of Reye’s syndrome.
7.1.4 Geriatrics
In general, ASA should be used with caution in elderly patients (≥ 60 years of age), as these patients may be more susceptible to adverse reactions.
8 ADVERSE REACTIONS
8.1 Adverse Reaction Overview
Many adverse reactions due to ASA ingestion are dose-related. The following is a list of adverse reactions that have been reported in the literature and from both clinical and post-marketing experience.
Gastrointestinal: (the frequency and severity of these adverse effects are dose-related): nausea, vomiting, diarrhea, gastrointestinal bleeding and/or ulceration, dyspepsia, heartburn, hematemesis, melena, abdominal pain, rarely gastrointestinal inflammation, and intestinal diaphragm disease with frequency not known (especially in long-term treatment).
Bleeding: Due to platelet inhibition, bleedings e.g., perioperative haemorrhage, hematomas, epistaxis, urogenital bleedings, and gingival bleedings may occur.
Serious bleedings, such as gastrointestinal tract hemorrhages, and cerebral hemorrhages are rare. Isolated cases of potentially life-threatening bleedings have been reported, especially in patients with uncontrolled hypertension and/or concomitant antihemostatic agents.
Ear: dizziness, tinnitus, vertigo, hearing loss. Dizziness and tinnitus have been reported, which may be indicative of an overdose.
Hematologic: leukopenia, thrombocytopenia, purpura, anemia. Anemia with respective laboratory and clinical signs and symptoms, such as asthenia, pallor, and hypoperfusion is generally caused by bleeding (e.g., occult microbleeding, acute or chronic bleeding). Hemolysis and hemolytic anemia in patients with severe forms of glucose-6-phosphate dehydrogenase (G6PD) deficiency has been reported.
Dermatologic and hypersensitivity: urticaria, pruritus, skin eruptions, asthma, anaphylaxis, edema, nasal congestion and rhinitus. Severe allergic reactions, including anaphylactic shock are very rarely reported.
Miscellaneous: mental confusion, drowsiness, sweating, thirst. Transient hepatic impairment with increase in liver transaminases has very rarely been reported. Renal impairment and acute renal failure have been reported.
9 DRUG INTERACTIONS
9.2 Drug Interactions Overview
ASA should be used with caution with other products that have anticoagulation or antiplatelet effects, as these effects may be potentiated. Drugs that bind to protein binding sites should also be used cautiously since ASA may displace drugs from their protein binding site.
9.3 Drug-Behavioural Interactions
Alcohol: Increased damage to gastrointestinal mucosa and prolonged bleeding time due to additive effects of acetylsalicylic acid and alcohol. Patients having 3 or more alcoholic drinks per day should consult their physician before use.
9.4 Drug-Drug Interactions
Methotrexate, used at doses of 15mg/week or more: Increased hematological toxicity of methotrexate (due to decreased renal clearance of methotrexate by anti-inflammatory agents in general and displacement of methotrexate from its plasma protein binding by salicylates). See 2 CONTRAINDICATIONS.
Methotrexate, used at 15mg/week or less: Salicylates may retard the elimination of methotrexate by decreasing renal clearance of methotrexate, displacing methotrexate from protein binding sites, and thereby increasing its hematological toxicity.
Anti-coagulants, thrombolytics / other inhibitors of platelet aggregation / hemostasis, e.g. warfarin, heparin: Caution is necessary when salicylates and anticoagulants, thrombolytics / other inhibitors of platelet aggregation / hemostasis prescribed concurrently, as salicylates can depress the concentration of prothrombin in the plasma, leading to an increased risk of bleeding.
Oral hypoglycemics, e.g., Insulin, sulfonylureas: large doses of salicylates have a hypoglycemic action and may enhance the effect of oral hypoglycemic agents. Diabetics receiving concurrent salicylate and hypoglycemic therapy should be monitored closely: reduction of the sulfonylurea hypoglycemic drug dosage may be necessary.
Diuretics: Diuretics in combination with acetylsalicylic acid at higher doses leads to decreased glomerular filtration via decreased prostaglandin synthesis. As a result, sodium excretion may be decreased by salicylate administration.
Uricosuric Agents: Salicylates in large doses are uricosuric agents; smaller amounts may depress uric acid clearance and thus decrease the uricosuric effects of other drugs.
Valproic Acid: Salicylates may alter valproic acid (VPA) metabolism and may displace VPA from protein binding sites, possibly intensifying the effects of VPA. Caution is recommended when VPA is administered concomitantly with salicylates.
Glucocorticoids (systemic), except hydrocortisone used as replacement therapy in Addison’s disease: Decreased blood salicylate levels during corticosteroid treatment and risk of salicylate overdose after this treatment is stopped via increased elimination of salicylates by corticosteroids. Concurrent use may increase the incidence of gastrointestinal bleeding and ulceration.
Angiotensin Converting Enzyme (ACE) Inhibitors: The hyponatremic and hypotensive effects of ACE inhibitors may be diminished by the concomitant administration of ASA due to its indirect effect on the renin-angiotensin conversion pathway (i.e., inhibition of vasodilatory prostaglandins leading to decreased glomerular filtration). The potential interaction may be related to the dose of ASA (3 g/day or more).
Selective Serotonin Re-uptake Inhibitors (SSRIs): Increased risk of upper gastrointestinal bleeding due to possibly synergistic effect.
Digoxin: Plasma concentrations of digoxin are increased due to a decrease in renal excretion.
NSAIDs:
- ASA and other NSAIDs: The use of other NSAIDs with salicylates may increase the risk of ulcers and gastrointestinal bleeding due to a synergistic effect.
- Ibuprofen: Ibuprofen can interfere with the anti-platelet effect of low dose ASA acid (81 to 325 mg per day). Long-term daily use of ibuprofen may render ASA less effective when used for cardioprotection and stroke prevention. To minimize this interaction, regular users of ibuprofen and of low-dose, immediate-release ASA should take the ibuprofen at least one hour after and 11 hours before the daily ASA dose. The use of delayed-release (e.g., enteric-coated) ASA is not recommended when using ibuprofen regularly.
- Naproxen: Naproxen may attenuate the irreversible platelet inhibition induced by acetylsalicylic acid. Clinical pharmacodynamic data suggest that concurrent (same day) naproxen sodium usage for more than one day consecutively inhibits the effect of low-dose acetylsalicylic acid on platelet activity and this inhibition may persist for up to several days after stopping naproxen sodium therapy. The clinical relevance of this interaction is not known. Treatment with naproxen, in patients with increased cardiovascular risk may limit the cardiovascular protection of acetylsalicylic acid (see 7 WARNINGS AND PRECAUTIONS).
Healthcare professionals should advise consumers and patients regarding the appropriate concomitant use of NSAIDs (i.e., ibuprofen or naproxen) and ASA.
9.5 Drug-Food Interactions
Interactions with food have not been established.
9.6 Drug-Herb Interactions
Interactions with herb have not been established.
9.7 Drug-Laboratory Test Interactions
Salicylates can produce changes in thyroid function tests.
10 CLINICAL PHARMACOLOGY
10.1 Mechanism of Action
ASA interferes with the production of prostaglandins in various organs and tissues through acetylation of the enzyme cyclo-oxygenase. Prostaglandins are themselves powerful irritants and produce headaches and pain on injection in man. Prostaglandins also appear to sensitize pain receptors to other noxious substances such as histamine and bradykinin. By preventing the synthesis and release of prostaglandins in inflammation, ASA may avert the sensitization of pain receptors.
The antipyretic activity of ASA is due to its ability to interfere with the production of prostaglandin E1 in the brain. Prostaglandin E1 is one of the most powerful pyretic agents known.
The inhibition of platelet aggregation by ASA is due to its ability to interfere with the production of thromboxane A2 within the platelet. Thromboxane A2 is, largely, responsible for the aggregating properties of platelets.
In vitro studies have shown that ASA enhances the activity of the Nitric oxide (NO)-cGMP system and heme oxygenase-1 (HO-1) by acting on endothelial NO synthase site.
10.2 Pharmacodynamics
Effects on platelets: relation to hemostasis and thrombosis.
Platelets play an important role in normal hemostasis and clinical pathologic and experimental evidence indicates that their aggregation may play an equally important role in the evolution of a variety of disease states including cerebrovascular disease, ischemic heart disease and myocardial infarction. ASA inhibits platelet aggregation by irreversibly acetylating platelet cyclo-oxygenase, thereby blocking the production of prostaglandin endoperoxides PGG2 and PGH2 which are precursors of the major platelet-aggregating material, thromboxane A2, which is also a powerful vasoconstrictor. However, ASA does not prevent the adherence of platelets to damaged vessel walls or the release of granule contents from these adherent platelets. As the anuclear platelets are unable to synthesize new enzyme molecules to replace those that have been inactivated, inhibition of platelet aggregation by ASA thus persists for the life of the platelets. Daily administration of 20 to 40 mg of ASA to healthy volunteers reduced platelet thromboxane production but inhibited platelet aggregation only partially. When administered to patients recovering from myocardial infarction, 50 mg ASA daily had the same effects on thromboxane production, platelet aggregation and bleeding times as 324 mg daily. Other studies show that ASA doses of 40 to 325 mg daily suppressed thromboxane production by at least 80%, but 80 mg ASA daily was the lowest dose required for maximum cumulative thrombocyte function inhibition. The protective effect of ASA against experimentally induced thrombosis or atherosclerosis has been demonstrated in several animal models.
Besides inhibiting the biosynthesis of thromboxane A2 by platelets, ASA also interferes with the production of prostacyclin (PGI2) by vascular endothelial cells, the above-mentioned prostaglandin endoperoxides being common precursors of both thromboxane A2 and prostacyclin. This latter compound is one of the most powerfully acting platelet deaggregators and vasodilators and thus it would appear that the interference with the hemostatic processes by ASA depends on the thromboxane-prostacyclin balance. In fact, it has been suggested that under some conditions, high doses of ASA may be thrombogenic. However, in contrast to platelets, the vascular endothelial cells are able to regenerate cyclo-oxygenase in a relatively short time and therefore therapeutic doses of ASA are likely to produce a lesser inhibition of the vascular prostacyclin system than of the platelet thromboxane-forming mechanism. In fact, there is no clinical evidence to indicate that high doses of ASA would result in an increased risk of thromboembolism. Indeed, quite the contrary was observed and, in a controlled study, paradoxical shortening of the bleeding time was not observed at a daily ASA dose of 3.6 g. Lower dosages of ASA make selective blocking of the TxA2-synthesis without a simultaneous blocking of PGI2-production possible.
The use of ASA in patients with a suspected acute myocardial infarction was investigated in a large multi-centre trial involving over 17,000 patients. Treatment with ASA resulted in a 23% reduction in the risk of vascular mortality versus placebo at 5 weeks. This use translates to a reduction of 24 deaths and 14 non-vascular events per 1000 patients treated.
The effect of time to therapy revealed that patients treated with ASA "early" (0 to 4 hours) versus "late" (5 to 24 hours) after symptom onset experienced reductions in the odds of vascular death of 25% versus 21%, versus placebo at 5 weeks. 'Early' treatment with ASA resulted in the saving of 4 additional lives per 1000 patients versus 'late' treatment.
Long term follow-up (up to 10 years) of patients in this study established that the early survival advantage to ASA persisted long term, and that this prolonged benefit was additive to that of fibrinolytic therapy.
The use of ASA for secondary prevention of thrombotic events is supported by a comprehensive overview of a number of clinical trials involving patients who already had some type of vascular disease (myocardial infarction, unstable angina, stroke or transient cerebral ischemia). Overall, these studies point to a 26 to 28% reduction of the combined endpoints of MI, stroke, or vascular deaths by treatment with ASA alone at doses of 75 to 325 mg daily. Studies which directly compared low doses with higher doses (30 to 1200 mg/day), indicated that the incidence of gastrointestinal adverse effects were significantly less common with the lower doses.
In a study in patients undergoing coronary artery bypass surgery (CABG), patients given ASA at a dosage of 80 mg to 650 mg within 48 hours of revascularization had a risk of dying reduced to 1.3% as compared to 4.0% for those who did not receive treatment (P<0.001). There was a reduction in the incidence of myocardial infarction of 2.8% vs. 5.4%, p < 0.001. In total, the reduction in fatal and non-fatal outcomes was lower in those who received ASA, 10.6% vs. 18.6% in those who did not (p<0.001). The investigators Perioperative Ischemia Research Group (PIRG) concluded that early use of ASA after coronary by-pass surgery is safe and is associated with a reduce risk of death and ischemic complications involving the heart, brain, kidneys and gastrointestinal tract.
There was no ASA dose effect observed for either fatal or non-fatal outcomes with total doses lower than 325mg daily.
Recent discussions have focused on the efficacy of ASA for the primary prevention of myocardial infarction and stroke. Two large scale randomized trials, aimed at evaluating prophylactic use of ASA, were conducted among apparently healthy male physicians (22,000 in the United States and 5,000 in the United Kingdom) and their results have been published. In the summary overview of the combined results presented by the principal investigators, the authors state that:
“Taken together, these two primary prevention studies demonstrate a significant (p < 0.0001) reduction in non-fatal myocardial infarction of about one third.”
On the other hand, the same two studies have not indicated any reduction in overall vascular mortality and also suggested a slight increase in the risk of non-fatal disabling stroke. Current controversy exists about the applicability of these findings, obtained in a selected population, to the general public. As well, the optimum dosage regimen still remains an open question in this regard. Thus, the use of ASA for primary prevention should remain, in the words of the principal investigators:
"a matter of judgment in which the physician considers the cardiovascular risk profile of the patient and balances the known hazards of ASA against the clearly established reduction in the incidence of a first myocardial infarction".
Effect of Ibuprofen on Platelet Aggregation, Bleeding and Clotting Times in Normal Volunteers.
Experimental data suggest that ibuprofen may inhibit the effect of low dose ASA (81 to 325 mg per day) on platelet aggregation when they are dosed concomitantly. In one study, when a single dose of ibuprofen 400mg was taken within 8 hours before or within 30 minutes after immediate release ASA dosing (81mg), a decreased effect of acetylsalicylic acid on the formation of thromboxane or platelet aggregation occurred. However, the limitations of these data and the uncertainties regarding extrapolation of ex vivo data to the clinical situation imply that no firm conclusions can be made for regular ibuprofen use, and no clinically relevant effect is considered to be likely for occasional ibuprofen use. In a more recent double blind, randomized, placebo-controlled trial with healthy subjects by Cryer et. al, 2005, it has been shown that the drug-drug interaction is absent when immediate release ASA (81 mg) was taken 1 hour before taking ibuprofen (400 mg, TID) and also when ibuprofen was given 11 hours before the intake of low dose ASA. Thus, in order to adequately minimize potential interaction, the recommended dosing schedule for immediate release low dose ASA is to wait at least 11 hours after or 1 hour before taking up to a 400mg dose of ibuprofen.
10.3 Pharmacokinetics
Absorption:
When ASA is taken orally, it is rapidly absorbed from the stomach and proximal small intestine. The gastric mucosa is permeable to the non-ionized form of acetylsalicylic acid, which passes through the stomach wall by a passive diffusion process.
Optimum absorption of salicylate in the human stomach occurs in the pH range of 2.15 to 4.10. Absorption in the small intestine occurs at a significantly faster rate than in the stomach. After an oral dose of 0.65 g ASA, the plasma acetylsalicylate concentration in man usually reaches a level between 0.6 and 1.0mg % in 20 minutes after ingestion and drops to 0.2 mg % within an hour. Within the same period of time, half or more of the ingested dose is hydrolyzed to salicylic acid by esterases in the gastrointestinal mucosa and the liver, the total plasma salicylate concentration reaching a peak between one or two hours after ingestion, averaging between 3 and 7mg %. Many factors influence the speed of absorption of ASA in a particular individual at a given time; tablet disintegration, solubility, particle size, gastric emptying time, psychological state, physical condition, nature and quantity of gastric contents, etc., all affect absorption.
Distribution:
Distribution of salicylate throughout most body fluids and tissues proceeds at a rapid rate after absorption. Aside from the plasma itself, fluids which have been found to contain substantial amounts of salicylate after oral ingestion include spinal, peritoneal and synovial fluids, saliva and milk. Tissues containing high concentrations of the drug are the kidney, liver, heart and lungs. Concentrations in the brain are usually low, and are minimal in feces, bile and sweat.
The drug readily crosses the placental barrier. At clinical concentrations, from 50% to 90% of the salicylate is bound to plasma proteins especially albumin, while acetylsalicylic acid itself is bound to only a very limited extent. However, ASA has the capacity of acetylating various proteins, hormones, DNA, platelets and hemoglobin, which at least partly explains its wide-ranging pharmacological actions.
Metabolism:
The liver appears to be the principal site for salicylate metabolism, although other tissues may also be involved. The three chief metabolic products of ASA or salicylic acid are salicyluric acid, the ether or phenolic glucuronide and the ester or acyl glucuronide. A small fraction is also converted to gentisic acid and other hydroxybenzoic acids. The half-life of ASA in the circulation is from 13 to 19 minutes so that the blood level drops quickly after absorption is complete. However, the half-life of the salicylate ranges between 3.5 and 4.5 hours, which means that 50% of the ingested dose leaves the circulation within that time.
Elimination:
Excretion of salicylates occurs principally via the kidney, through a combination of glomerular filtration and tubular excretion, in the form of free salicylic acid, salicyluric acid, as well as phenolic and acyl glucuronides. Salicylate can be detected in the urine shortly after its ingestion but the full dose requires up to 48 hours for complete elimination. The rate of excretion of free salicylate is extremely variable, reported recovery rates in human urine ranging from 10% to 85%, depending largely on urinary pH. In general, it can be stated that acid urine facilitates reabsorption of salicylate by renal tubules, while alkaline urine promotes excretion of the drug.
With the administration of 325mg, elimination of ASA is linear following a first order kinetics. At high concentrations, elimination half life increases.
Special Populations and Conditions
Absorption and clearance of salicylates are not affected by gender or age.
11 STORAGE, STABILITY AND DISPOSAL
Store between 15°C to 30°C.
12 SPECIAL HANDLING INSTRUCTIONS
None
PART II: SCIENTIFIC INFORMATION
13 PHARMACEUTICAL INFORMATION
Drug Substance
Proper name: acetylsalicylic acid
Chemical name: 2-(Acetyloxy) benzoic acid; salicylic acid acetate
Molecular formula and molecular mass: C9H8O4, 180.16 g/mol
Structural formula:
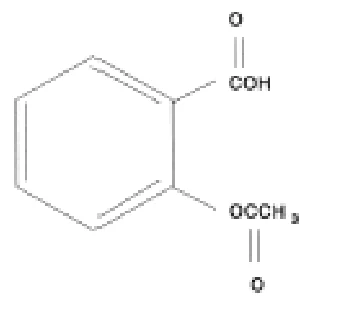
Physicochemical properties:
Description: White granular powder.
Solubility: Solubility in common solvents at 25°C:
| Solvent | Solubility (parts of solvent required for 1 part of solute) | Descriptive Term (as defined in the USP) |
|---|---|---|
| Alcohol | From 1 to 10 | Freely soluble |
| Chloroform / Ether | From 10 to 30 | Soluble |
| Absolute Ether | From 30 to 100 | Sparingly soluble |
| Water | From 100 to 1000 | Slightly soluble |
Solubility in 0.1N HCL
| °C | mg/mL |
|---|---|
| 30°C | 4.25 |
| 37°C | 5.65 |
| 50°C | 8.8 |
pK value (25°C): 3.49
Melting Point: 135°C (rapid heating)
14 CLINICAL TRIALS
14.1 Trial Design and Study Demographics
Table 2 - Summary of patient demographics for clinical trials in reducing the risk of vascular mortality in patients with a suspected acute myocardial infarction
| Study # | Study design | Dosage, route of administration and duration | Study subjects (n) | Mean age (Range) | Sex |
ISIS – 2 ISIS, 1998 | Multicentre international 2x2 factorial, randomized, placebo controlled study. | 160-162.5 mg oral for 30 days after suspected acute MI. (Median follow-up to 15 months). | ASA 8587, Streptokinase 8592, ASA + Strep 4292, Placebo 4300 | Not available | Not available |
Table 3 - Summary of patient demographics for clinical trials in reducing the risk of a first non-fatal myocardial infarction in individuals deemed to be at sufficient risk of such an event by their physician
| Study # | Study design | Dosage, route of administration and duration | Study subjects (n) | Mean age (Range) | Sex |
TPT Medical Research Council’s General Practice Research Framewo rk, 1998 | Randomized, factorial, placebo-controlled, parallel-group study | warfarin (mean) 4.1mg, ASA 75mg | warfarin + ASA 1,277 warfarin + ASA placebo 1,268 ASA + warfarin placebo 1,268 ASA placebo + warfarin placebo 1,272 | 45-69 years | Male |
HOT Hansson et al, 1998 | Prospective, randomized, open with blinded endpoint evaluation (PROBE). ASA component was | ASA 75mg or placebo; felodipine 5mg, ACE-inhibitors, β- blockers, diuretics mean - 3.8 years | 19,567 subjects of which 18,790 were randomized to ASA or Placebo | 61.5 years
| Male 53% Female 47% |
| Study # | Study design | Dosage, route of administration and duration | Study subjects (n) | Mean age (Range) | Sex |
| double blinded | (ASA = 9,399; Placebo = 9,391) | ||||
PHS Steering Committee of the Physician s’ Health Study Research Group, 1989 | Double blind placebo controlled, 2x2 factorial randomized parallel group | ASA 325mg every other day for 60.2 months | 22,071 ASA = 11,037 Placebo = 11,034 | 40 to 84 years | Male |
Table 4 - Summary of patient demographics for clinical trials in reducing the risk of morbidity and death in patients with unstable angina and in those with previous myocardial infarction
| Study # | Study design | Dosage, route of administration and duration | Study subjects (n) | Mean age (Range) | Sex |
RISC 1990 | Prospective randomized, double blind, placebo controlled, multicentre study | ASA 75mg daily for 3 months after initial heparin by IV for 5 days |
| 58 years | Male |
RISC Trial, 12 month follow-up 1990 | Prospective randomized, double blind, placebo controlled, multicentre study | ASA 75mg daily for 3 months after initial IV heparin for 5 days |
| 58 years | Male |
Verheugt et al. 1990 | Prospective, randomized, placebo-controlled, comparative multicentre study | ASA 100mg for approx. 3 months | ASA 50 Placebo 50 | ASA 61 years Placebo 64 years | ASA 72% male Placebo 76% male |
| Study # | Study design | Dosage, route of administration and duration | Study subjects (n) | Mean age (Range) | Sex |
| SAPAT 1992 | Prospective, randomized, double blind placebo controlled, multicentered study | ASA 75mg daily for up to 6 years (median 50 months) | ASA 1009 Placebo 1026 | 52 years | ASA male 51% Placebo males 53% |
Table 5 - Summary of patient demographics for clinical trials in reducing the risk of transient ischemic attacks (TIA) and for secondary prevention of atherothrombotic cerebral infarction
| Study # | Study design | Dosage, route of administration and duration | Study subjects (n) | Mean age (Range) | Sex |
|---|---|---|---|---|---|
SALT 1991 | Prospective, randomized, double blind, placebo controlled, multicentre study | ASA 75mg daily for minimum of 12 months and maximum of 63 months (mean 30.6 months) | ASA 676 Placebo 684 | 50-79 years ASA mean: 67 years PLA mean: 66.8 years | ASA 65.4% male Placebo 66.2% male |
Lindblad et al. 1993 | Prospective, randomized, double blind placebo controlled study | ASA 75mg daily for 6 months | ASA 117 Placebo 115 | 66 years (40-81 years) | 75% male |
14.2 Study Results
Table 6 - Results of ISIS-2 Study in reducing the risk of vascular mortality in patients with a suspected acute myocardial infarction.
| Primary Endpoints | Associated value and statistical significance for Drug at specific dosages | Associated value and statistical significance for Placebo or active control |
|---|---|---|
| Vascular death after 5- week period | ASA 9.4%, Placebo 11.8% Odds reduction 23% | ASA vs. Placebo 2p < 0.00001 ASA was statistically significantly better than placebo |
Table 7 - Results of studies; TPT, HOT & PHS in reducing the risk of a first non-fatal myocardial infarction in individuals deemed to be at sufficient risk of such an event by their physician
| Primary Endpoints | Associated value and statistical significance for Drug at specific dosages | Associated value and statistical significance for Placebo or active control |
|---|---|---|
Study: TPT All ischemic heart disease defined as the sum of fatal and non-fatal events (i.e. coronary death and fatal and non-fatal myocardial infarction). | ASA 10.2%, Placebo 13.3% 20% reduction in IHD | p = 0.04 ASA was statistically significantly better than placebo |
Study: HOT Major cardiovascular events were defined as all (fatal and non-fatal) myocardial infarctions, all (fatal and non- fatal) strokes, and all other cardiovascular deaths. | Reduction in all cardiovascular events by 15% and all myocardial infarction by 36% | p=0.03 p = 0.002 ASA was statistically significantly better than placebo |
Study: PHS fatal and non-fatal myocardial infarction | 325 mg ASA every other day: 44% reduction in risk of MI in ASA vs. Placebo group Relative Risk 0.56, 95% CI 0.45-0.70 | p<0.00001 P<0.0001 ASA was statistically significantly better than placebo |
Table 8: Results of studies; RISC, RISC Trial 12-month follow-up, Verheugt et al & SAPAT in reducing the risk of morbidity and death in patients with unstable angina and in those with previous myocardial infraction
| Primary Endpoints | Associated value and statistical significance for Drug at specific dosages | Associated value and statistical significance for Placebo or active control |
|---|---|---|
Study: RISC Death or non-fatal MI | 5 days: Risk Ratio 0.43 (CI 0.21-0.91) 30 days: Risk Ratio 0.31 (CI 0.18-0.53) 90 days: Risk Ratio 0.36 (0.21-0.57) | p=0.03 p<0.0001 p<0.0001 ASA was statistically significantly better than placebo ASA vs Comparator: Heparin was not statistically significantly better than placebo and there was no comparison to ASA |
Study: RISC Trial 12-month follow-up MI and death | 6 months: ASA-35 events, heparin 76 events. Risk Ratio 0.46 (CI 0.31- 0.67) 12 months, ASA 44 events, heparin 85 events. Risk Ratio 0.52 (CI 0.37-0.72) | p<0.0001 p=0.0001 ASA was statistically significantly better than placebo |
Study: Verheugt et al. Reinfarction rate | ASA 2 patients (4%), Placebo 9 patients (18%) | p<0.03 ASA was statistically significantly better than placebo |
Study: SAPAT non-fatal or fatal MI or sudden death | ASA 8%, Placebo 12% | p=0.003 ASA was statistically significantly better than placebo |
Table 9 - Results of studies; SALT & Linblad et al in reducing the risk of transient ischemic attacks (TIA) and for secondary prevention of atherothrombotic cerebral infarction
| Primary Endpoints | Associated value and statistical significance for Drug at specific dosages | Associated value and statistical significance for Placebo or active control |
|---|---|---|
SALT Risk of stroke or death | 18 % reduction in risk: Relative Risk 0.82 (CI 0.67-0.99) | p=0.02 ASA was statistically significantly better than placebo |
| Primary Endpoints | Associated value and statistical significance for Drug at specific dosages | Associated value and statistical significance for Placebo or active control |
|---|---|---|
Lindblad et al Stroke (without complete recovery) at 6 months | ASA 2 cases, Placebo 11 cases | p=0.01 ASA was statistically significantly better than placebo |
14.3 Comparative Bioavailability Studies
A comparative bioavailability study was performed on healthy male human volunteers under fasting conditions. The rate and extent of absorption of salicylic acid was measured and compared following a single oral dose of COATED DAILY LOW DOSE ASA 81 mg (acetylsalicylic acid) and ASPIRIN® 81mg Delayed Release tablets. The results from measured data are summarized in the following table:
Salicylic Acid (n=23) 3 x 81 mg ASA (acetylsalicylic acid) Enteric Coated Tablets - Fasted State From measured data uncorrected for potency Geometric Mean Arithmetic Mean (CV %) | ||||
| Parameter | COATED DAILY LOW DOSE ASA 81 mg Test | ASPIRIN®€ Reference | % Ratio of Geometric Means# | 90% Confidence Interval# |
AUCT (ng·h/mL) | 52449 53188 (17) | 54697 55738 (20) | 95.9 | 93.3 – 98.5 |
AUCI (ng·h/mL) | 53836 54691 (18) | 55722 56873 (21) | 96.6 | 94.0 – 99.3 |
Cmax (ng/mL) | 10220 10317 (14) | 11330 11490 (17) | 89.9 | 84.9 – 95.2 |
Tmax§ (h) | 5.39 (16) | 4.59 (19) | ||
T1/2§ (h) | 2.10 (15) | 2.03 (15) | ||
€ ASPIRIN® Coated Daily Low Dose (acetylsalicylic acid) 81 mg enteric coated tablets, Bayer Canada, purchased in Canada.
§ Expressed as the arithmetic mean (CV%) only.
# based on least squares estimates.
15 MICROBIOLOGY
No microbiological information is required for this drug product.
16 NON-CLINICAL TOXICOLOGY
General Toxicology:
The clinical and pathological signs of poisoning from toxic and lethal oral doses of ASA have been extensively described for man, much less extensively for other species.
The acute toxicity of ASA in animals has been studied and reviewed in detail by Boyd. The signs of poisoning in rats from doses in the lethal range are due to varying degrees of gastroenteritis, hepatitis, nephritis, pulmonary edema, encephalopathy, shock and minor toxic effects on other organs and tissues. Death is due to convulsions or cardiovascular shock. The major difference between species appears to be the ability to vomit toxic doses seen in man, cats and dogs, but not in mice, rats and rabbits. Otherwise, the pathological reaction to toxic doses of ASA is similar in all species in which such studies have been reported. The acute oral LD50 values have been reported as being over 1.0 g/kg in man, cat and dog, 0.92 g/kg in female and 1.48 g/kg in male albino rats, 1.19 g/kg in guinea pig, 1.1 g/kg in mouse and 1.8 g/kg in rabbit.
Chronic toxicity studies were reported in mice and rats. When ASA was administered at 2 to 20 times the maximum tolerated clinical dose to mice for up to one year, a dose-related deleterious effect was observed on mean survival time, number of young born and number of young raised to weaning age. No evidence of carcinogenic effect was found.
The chronic oral LD50 in male albino rats has been reported as 0.24 g/kg/day when given for 100 days. At these daily doses ASA produced no anorexia and no loss of body weight. It did produce polydipsia, aciduria, diuresis, drowsiness, hyperreflexia, piloerection, rapid and deep respiration, tachycardia, and during the second month, soft stools, epistaxis, sialorrhea, dacryorrhea and death in hypothermic coma. Autopsy disclosed the presence of a hypertrophied stomach, renal congestion, mild hepatitis and pneumonitis. While teratogenic effects were noted in animals at near lethal doses, there is no evidence to indicate that ASA is teratogenic in man.
17 SUPPORTING PRODUCT MONOGRAPHS
- 1. ASPIRIN® Regular Strength (acetylsalicylic acid tablets USP, 325mg), ASPIRIN® Extra Strength (acetylsalicylic acid tablets USP, 500mg), ASPIRIN® 81mg (acetylsalicylic acid delayed release tablets USP, 81mg) and ASPIRIN® 81mg Quick Chews® (acetylsalicylic acid tablets USP, 81mg), submission control 280158, Product Monograph, Bayer Inc. (JUL 15, 2024)