


Product Monograph - Apo-Dipyridamole-SC Tab 25mg
SUMMARY PRODUCT INFORMATION
| Route of Administration | Dosage Form / Strength | All Nonmedicinal Ingredients |
| Oral | APO-DIPYRIDAMOLE Tablets 25 mg, 50 mg, 75 mg and 100 mg APO-DIPYRIDAMOLE SC Tablets 25 mg, 50 mg, 75 mg | Microcrystalline cellulose, magnesium stearate, colloidal silicon dioxide, hydroxypropyl methylcellulose, polyethylene glycol, titanium dioxide (except the 75 mg tablet), and FD&C yellow #6. The 50 mg tablets also contain the non-medicinal ingredients ferric oxide yellow and ferric oxide red. The 75 mg tablets also contain the non-medicinal ingredients D&C red #7 and carnauba wax Microcrystalline cellulose, magnesium stearate, colloidal silicon dioxide, sucrose, shellac, titanium dioxide, carnauba wax, white wax, and FD&C yellow #6, yellow ferric oxide and red ferric oxide. |
INDICATIONS AND CLINICAL USE
Thromboembolic Disease
APO-DIPYRIDAMOLE (dipyridamole) tablets are indicated for:
- The prevention of post-operative thromboembolic complications associated with prosthetic heart valve.
CONTRAINDICATIONS
- Patients who are hypersensitive to this drug or to any ingredient in the formulation or component of the container. For a complete listing, see the Dosage Forms, Composition and Packaging section of the product monograph.
WARNINGS AND PRECAUTIONS
Cardiovascular
Since excessive doses of dipyridamole (intravenous or oral) or intravenous doses given too rapidly can produce peripheral vasodilation, APO-DIPYRIDAMOLE should be used with caution in patients with hypotension, coronary artery disease, including rapidly worsening angina, left ventricular outflow obstruction, (including subvalvular aortic stenosis), or hemodynamic instability. In rare cases, such patients may be at risk for developing myocardial ischemia and infarction.
Clinical experience suggests that patients being treated with oral dipyridamole who also require pharmacological stress testing with intravenous dipyridamole, should discontinue drugs containing oral dipyridamole for twenty-four hours prior to stress testing. Failure to do so may impair the sensitivity of the test.
In the case of severe hypotension, the patient should be placed in a supine position with the head tilted down if necessary, before administration of parenteral aminophylline. If 250 mg of aminophylline does not relieve chest pain symptoms within a few minutes, sublingual nitroglycerin may be administered. If chest pain continues despite use of aminophylline and nitroglycerin, the possibility of myocardial infarction should be considered. If the clinical condition of a patient with an adverse event permits a one minute delay in the administration of parenteral aminophylline, thallium-201 may be injected and allowed to circulate for one minute before the injection of aminophylline. This will allow initial thallium perfusion imaging to be performed before reversal of the pharmacologic effects of APO-DIPYRIDAMOLE on the coronary circulation.
Hepatic/Biliary/Pancreatic
A small number of cases have been reported in which unconjugated dipyridamole was shown to be incorporated into gallstones to a variable extent (up to 70% by dry weight of stone). These patients were all elderly, had evidence of ascending cholangitis and had been treated with oral dipyridamole for a number of years. There is no evidence that dipyridamole was the initiating factor in causing gallstones to form in these patients. It is possible that bacterial deglucuronidation of conjugated dipyridamole in bile may be the mechanism responsible for the presence of dipyridamole in gallstones.
Special Populations
Pregnant Women: Reproductive studies have been performed in mice, rats, and rabbits at doses of up to 125 mg/kg and have not revealed evidence of impaired embryonic development attributable to dipyridamole. However, there have not been adequate, well controlled studies in pregnant women and the drug should be used during pregnancy only if the expected benefits outweigh the potential risks.
Nursing Women: Dipyridamole is excreted in human milk. Caution should therefore be used when this drug is administered to nursing mothers.
Pediatrics: The safety and effectiveness of dipyridamole have not been established in the pediatric population.
ADVERSE REACTIONS
Clinical Trial Adverse Drug Reactions
Because clinical trials are conducted under very specific conditions the adverse reaction rates observed in the clinical trials may not reflect the rates observed in practice and should not be compared to the rates in the clinical trials of another drug. Adverse drug reaction information from clinical trials is useful for identifying drug-related adverse events and for approximating rates.
Adverse reactions at therapeutic doses are usually minimal and transient. Occasionally diarrhoea, vomiting, headache, dizziness, nausea, flushing, syncope or weakness, myalgia, and skin rash have occurred during initiation of therapy. Mild occasional gastric distress can be avoided by administration of the tablets with a glass of milk. Gastric irritation, emesis and abdominal cramping may occur at high dosage levels. Rare cases of what appears to be an aggravation of angina pectoris have been reported, usually at the initiation of therapy.
On those uncommon occasions when adverse reactions have been persistent or intolerable to the patient, withdrawal of the medication has been followed promptly by cessation of the undesirable symptoms.
When dipyridamole is used in combination with ASA, the only side effect clearly attributable to dipyridamole is headache. This symptom shows an increase of 5.5% in the combination treated group over that occurring in a group of patients treated with ASA alone. Other adverse reactions which occur during combination therapy are similar to those mentioned above, together with the well documented side effects of ASA therapy, notably gastric distress and gastrointestinal bleeding.
At the higher doses of dipyridamole there may be an increase in the incidence of adverse reactions.
In very rare cases, increased bleeding during or after surgery has been reported.
Post-Market Adverse Drug Reactions
As a result of its vasodilator properties, dipyridamole may cause hypotension, hot flushes, and tachycardia. Worsening of symptoms of coronary heart disease has been observed. Hypersensitivity reactions such as rash, urticaria, severe bronchospasm and angio-oedema have been reported. Dipyridamole has been shown to be incorporated into gallstones (See Warnings).
Isolated cases of thrombocytopenia have been reported in conjunction with treatment with dipyridamole.
DRUG INTERACTIONS
Drug-Drug Interactions
Table 1- Established or Potential Drug-Drug Interactions
| Dipyridamole | Effects | Clinical Comments |
| Dipyridamole - Adenosine | Dipyridamole increases plasma levels and cardiovascular effects of adenosine. | Adjustment of adenosine dosage should be considered. |
Dipyridamole - Anticoagulants, thrombolytics | the combined use of such agents may result in an increased risk of hemorrhage. | Caution is necessary when dipyridamole is used concurrently with anticoagulants or thrombolytics. |
| Dipyridamole - ASA | the addition of dipyridamole to acetylsalicylic acid does not increase the incidence of bleeding events. | |
| Dipyridamole - Warfarin | When dipyridamole was administered concomitantly with warfarin, bleeding was no greater in frequency or severity than that observed when warfarin was |
| administered alone. | ||
| Dipyridamole – Blood pressure lowering drugs | Dipyridamole may increase the hypotensive effect of blood pressure lowering drugs. | |
| Dipyridamole – Cholinesterase inhibitors | Dipyridamole may counteract the anticholinesterase effect of cholinesterase inhibitors. | In patients with myasthenia gravis, readjustment of therapy may be necessary during treatment with dipyridamole. |
Drug-Food Interactions
Xanthine derivatives (e.g., found in coffee, tea) may weaken the effect of APO-DIPYRIDAMOLE and therefore should be avoided 24 hours before myocardial imaging with dipyridamole.
DOSAGE AND ADMINISTRATION
Dosing Considerations
Thromboembolic Disease
Recommended Dose and Dosage Adjustment
The recommended oral dose is 100 mg q.i.d., one hour before meals. The maximum daily dose is 600 mg. A lower dose of 100 mg of APO-DIPYEIDAMOL (dipyridamole) daily together with 1 g ASA daily, prolongs platelet survival to the same extent.
OVERDOSAGE
Hypotension, if it occurs, is likely to be of short duration but vasopressor substances may be used if necessary. Symptoms such as feeling warm, flushes, sweating, accelerated pulse, restlessness, feeling of weakness and dizziness, and anginal complaints may occur. A drop in blood pressure and tachycardia might be observed.
Symptomatic therapy is recommended. A gastric decontamination procedure should be considered. Administration of xanthine derivatives (e.g. aminophylline) may reverse the haemodynamic effects of dipyridamole overdose. Due to its wide distribution to tissues and its predominantly hepatic elimination, dipyridamole is not likely to be accessible to enhanced removal procedures.
| For management of a suspected drug overdose, contact your regional poison control centre. |
ACTION AND CLINICAL PHARMACOLOGY
Mechanism of Action
Dipyridamole normalizes increased platelet adhesiveness and tendency to aggregate (Hellem's Method). Dipyridamole has been found to lengthen abnormally shortened platelet survival time in a dose-dependent manner; 400 mg/day or 100 mg/day plus 1 gram ASA.
It is believed that platelet reactivity and interaction with prosthetic cardiac valve surfaces, resulting in abnormal shortened platelet survival time is a significant factor in connection with prosthetic heart valve replacement.
In a controlled clinical trial involving patients who had undergone surgical placement of prosthetic heart valves (mitral and/or aortic valve replacement), dipyridamole, in combination with anticoagulants, significantly decreased the incidence of post-operative thromboembolic events, without increasing hemorrhagic complications. The incidence of thromboembolic events in patients receiving dipyridamole in a dose of 400 mg/day in combination with anticoagulants was 1.3% compared to 14.3% to the control group treated with anticoagulant alone.
In vitro dipyridamole potentiates the aggregation-inhibiting effects of adenosine and prostaglandin E1, inhibits platelet uptake of adenosine, serotonin and glucose, and increases platelet cyclic AMP levels. At higher concentrations dipyridamole inhibits platelet aggregation induced by ADP or collagen.
Myocardial blood flow increases in a dose-dependent fashion after oral dipyridamole, with flows 170% or more above normal. Maximal increases are achieved at about 2.0 µg/mL with 0.8 µg/mL being the threshold serum level. Single oral doses of 150 mg dipyridamole produce the maximal response. At normal therapeutic doses, no significant alterations of peripheral blood flow, systemic blood pressure, or heart rate have been observed.
Pharmacodynamics
Dipyridamole is a coronary vasodilator in man. The mechanism of vasodilation has not been fully elucidated, but may result from inhibition of uptake of adenosine, an important mediator of coronary vasodilation. The vasodilatory effects of dipyridamole are abolished by administration of the adenosine receptor antagonist theophylline.
Pharmacokinetics
Absorption: Dipyridamole is readily absorbed from the gastrointestinal tract, reaching peak plasma levels in man 1-3 hours following oral administration. Peak plasma levels are dose-dependent and range from about 0.5 mcg/mL after a 25 mg dose to 1.6 mcg/mL after a 75 mg dose. Blood levels are quite variable, possibly depending on food intake and gastrointestinal peristalsis. Ingestion on an empty stomach may result in higher blood levels.
Distribution:
After oral administration about 3 hours of 20 to 50 mg, plasma levels decline
tri-exponentially with half-lives of 5 minutes (i.v. only), 53 minutes and about 10-12 hours.
The volume of distribution is about 140 litres with about 92-99% binding to plasma proteins, primarily alpha1-acid glycoprotein.
STORAGE AND STABILITY
Store at room temperature, 15°C to 30°C.
DOSAGE FORMS, COMPOSITION AND PACKAGING
APO-DIPYRIDAMOLE 25 mg: each orange, round, biconvex, film-coated tablet engraved “25” on one side contains 25 mg of dipyridamole. Available in bottles of 100, 500 and 1000.
APO-DIPYRIDAMOLE 50 mg: each brown, round, biconvex, film-coated tablet engraved “D50” on one side contains 50 mg of dipyridamole. Available in bottles of 100, 500 and 1000.
APO-DIPYRIDAMOLE 75 mg: each orange-red, round, biconvex, film-coated tablet engraved “D75” on one side contains 75 mg of dipyridamole. Available in bottles of 100 and 500.
APO-DIPYRIDAMOLE 100 mg: each white, round, biconvex, film-coated tablet engraved “100” on one side contains 100 mg of dipyridamole. Available in bottles of 100.
APO-DIPYRIDAMOLE-SC (dipyridamole) is available as sugar-coated tablets containing:
APO-DIPYRIDAMOLE-SC 25 mg: orange, round, biconvex, sugar-coated tablet, both side plain. Available in bottles of 100 and 500.
APO-DIPYRIDAMOLE-SC 50 mg: brown, round, biconvex, sugar-coated tablet, both side plain. Available in bottles of 100 and 500.
APO-DIPYRIDAMOLE-SC 75 mg: orange-red, round, biconvex, sugar-coated tablet, both side plain. Available in bottles of 100 and 500.
Composition
Apo-Dipyridamole: In addition to dipyridamole, each film-coated tablet contains the non-medicinal ingredients microcrystalline cellulose, magnesium stearate, colloidal silicon dioxide, hydroxypropyl methylcellulose, polyethylene glycol, titanium dioxide (except the 75 mg tablet), and FD&C yellow #6. The 50 mg tablets also contain the non-medicinal ingredients yellow ferric oxide and red ferric oxide. The 75 mg tablets also contain the non-medicinal ingredients D&C red #7 and carnauba wax.
Apo-Dipyridamole-SC: In addition to dipyridamole, each sugar-coated tablet contains the non-medicinal ingredients microcrystalline cellulose, magnesium stearate, colloidal silicon dioxide, sucrose, shellac, titanium dioxide, carnauba wax, white wax and FD&C yellow #6. The 50 mg tablets also contain the non-medicinal ingredients yellow ferric oxide and red ferric oxide.
PART II: SCIENTIFIC INFORMATION
PHARMACEUTICAL INFORMATION
Drug Substance
Proper/Common Name: Dipyridamole
Chemical Name: 2,6-bis(diethanol-amino)-4,8 dipiperidino-pyrimido [5,4-d]-pyrimidine.
Structural Formula:
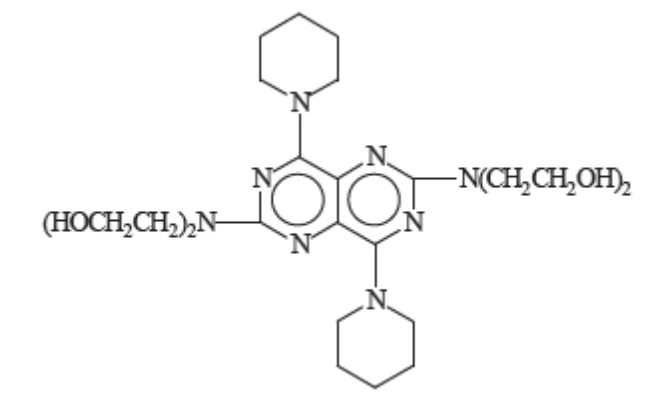
Molecular Formula: C24H40N8O4 Molecular Weight: 504.6 g/mol
Melting Range: 164 - 168°C
Description: Dipyridamole is a homogeneous yellow crystalline powder, odourless but with a bitter taste. It is soluble in dilute acids, methanol, ethanol and chloroform. In solution, dipyridamole is yellow and shows a strong blue-green fluorescence.
.
CLINICAL TRIALS
In a randomized, double-blind study, the effects of combined dipyridamole and ASA treatment were compared to ASA alone and to placebo in 2026 patients who had suffered a myocardial infarction 8 weeks to 5 years previously.
Combined treatment with dipyridamole 75 mg and ASA 325 mg t.i.d., reduced the life table rates for coronary incidence over a range of 37.0 to 66.7% when compared to placebo in the 4 to 24 month period after starting treatment. Similarly, for ASA alone, these reductions ranged from 29.1 to 51.4% over the same period. The differences between dipyridamole -ASA treatment and placebo were statistically significant at each 4 monthly evaluation.
Differences between ASA alone and placebo were statistically significant only at 8 and 24 months. At the end of the follow-up, 41 months later, essentially no differences were found between ASA and dipyridamole-ASA treatment but both drug treated groups showed 21 to 25% lower coronary mortality and coronary incidence compared to placebo. This was no longer statistically significant.
Hospitalization longer than 2 weeks for recurrent myocardial infarction was significantly reduced in both drug treatment groups compared to the placebo group.
The patient subgroup (447 or about 20% of the total sample) entering the trial within 6 months after their last myocardial infarction showed the largest reduction in total and coronary mortality. However, the only statistically significant finding was a 63.6% reduction in life table rates for coronary death in the dipyridamole /ASA group compared to placebo after 36 months of treatment.
A randomized, double-blind trial comparing dipyridamole (begun two days before operation) plus ASA (begun seven hours after operation) against placebo, in 407 patients undergoing coronary bypass, showed a statistically significant reduction in the rate of graft occlusion in patients receiving dipyridamole and ASA. Long-term follow-up showed that treatment with dipyridamole and ASA continued to be effective in preventing late development of vein graft occlusion after operation, and such treatment should be continued for at least one year. Use of dipyridamol pre-operatively in the prevention of bypass vein graft occlusion has not been associated with an increase of chest tube blood loss or transfusion requirements following coronary bypass surgery.
DETAILED PHARMACOLOGY
Pharmacokinetics
In animal studies, autoradiography in rats shows the liver with the highest concentrations of dipyridamole, with decreasing quantities in the following tissues: adrenal cortex, kidneys, myocardium, pituitary, skeletal muscle, lungs and blood. Twice as much drug is found in the myocardium as in skeletal muscle. Within the myocardium, the largest portion of dipyridamole is intracellular with the sarcolemma fraction containing up to 50%. On the basis of autoradiography, there are only small amounts of placental transfer. The drug does not cross the blood-brain barrier.
Conjugation of dipyridamole with glucuronic acid is the primary pathway of metabolism. In individuals with surgical drainage of the biliary tract, 95% of an intravenous 25 mg dose can be recovered from the bile within 2 hours. Enterohepatic circulation has been demonstrated in both animals and man.
Pharmacodynamics
Antithrombotic Effects
The effects of dipyridamole on platelet function may be due to its inhibition of cyclic AMP- phosphodiesterase activity or to potentiation of the effect of prostacyclin. Both of these pathways would lead to an intracellular increase of cyclic AMP, which prevents platelet clumping. Dipyridamole decreases platelet consumption and thrombosis associated with grafts and with the presence of foreign surfaces in the cardiovascular systems of experimental animals.
Teflon vascular prosthesis implanted in the superior vena cava of control dogs are coated with thrombotic deposits as early as 10 days following surgery. No thrombotic occlusions were observed 9 days or 6 months after surgery in dogs treated with dipyridamole 1 mg/kg/day, intravenously. At 18 months, prosthesis were coated with a thin layer of non-stenosing “neointima” without accumulation of thrombotic material.
In primates, platelet survival shortened by arteriovenous cannulation or homocystine injection can be normalized by dipyridamole, 100 mg/day, or 25 mg/day plus 300 mg/day ASA. ASA alone had no effect. Decreased platelet counts in control pigs undergoing cardiopulmonary bypass are less pronounced if the animals are treated with dipyridamole 10 mg/kg.
Thrombosis and neointimal fibrous hyperplasia (NFH) have been implicated as the major reasons for occlusion of the arterial grafts. The operation causes intimal injury at the anastomotic site, promoting platelet adherence at this site or within the graft itself; it triggers platelet aggregation and eventual occlusion by a platelet-fibrin thrombus. In addition, fibrous hyperplasia is possibly induced by a platelet-derived growth factor (PDGF). In studies with dogs, treatment with dipyridamole (started before CABG surgery and continued post-operatively) with the addition of aspirin (begun after surgery) has been shown to be effective in preventing early platelet deposition on grafts, early graft occlusion by thrombosis and possibly late graft narrowing by intimal hyperplasia.
Circulatory Effects:
The effects of endogenous adenosine are potentiated by dipyridamole inhibition of adenosine uptake in erythrocytes and platelets. Since adenosine is involved in physiological regulation of coronary blood flow, the coronary vasodilation induced by dipyridamole may be related to the adenosine-sparing effect of this drug.
Intravenous injection of dipyridamole in the dog causes coronary vasodilation. The threshold dose is 0.01 mg/kg with maximal effects reached by 0.2 mg/kg. A fall in systemic blood pressure, due to peripheral vasodilation, can be detected at a dose of 0.5 mg/kg with variable but not major effects on heart rate. The diastolic pressure decrease is larger than that for systolic pressure. The respiratory rate and depth are slightly increased, probably due to stimulation of carotid sinus chemoreceptors. An oral dose of 2.0 mg/kg in the dog increases coronary blood flow by 246% for 5 hours.
In the presence of aneroid ring constriction of coronary vessels, chronic administration of dipyridamole in dogs, rabbits and pigs increases the number and diameter of collateral coronary vessels. The rate of mortality in these animals is decreased compared to non-drug treated controls. Even in the absence of a chronic hypoxic stimulus, chronic dipyridamole treatment produces greater flow across intercoronary vessels in response to acute ligation of a coronary mainstem artery, compared to controls. When blood flow through ischemic areas was measured in experimentally produced infarctions, acute intravenous dipyridamole has produced both increases and decreases, as well as no change in flow. Intravenous dipyridamole, 10 mg/hr for 6 hours, decreased the size of experimental infarctions in dogs by 76% compared to saline-treated controls.
TOXICOLOGY
Acute Toxicity of Dipyridamole, ASA and their Combination
| Substance | Species | Route of Administration | LD50 (mg/kg) |
| dipyridamole | rat | p. o. | 6000 |
| rat | i. v. | 200 | |
| dog | p. o. | 400 | |
| acetylsalicylic acid (ASA) | rat | p. o. | 1820 |
| dog | p. o. | 1000 | |
| dipyridamole/ASA* | mouse (male) | p. o. | 3000-5000 |
| mouse (female) | p. o. | 5000 | |
| rat (male) | p. o. | 5000 | |
| rat (female) | p. o. | 5000 | |
| mouse (male) | i.p. | 910 | |
| mouse (female) | i.p. | 1200 | |
| rat (male) | i.p. | 1050 | |
| rat (female) | i.p. | 1230 | |
| dog | p. o. | 875-950 |
*dipyridamole/ASA mixed in a ratio of 1/5, weight/weight
After administration of dipyridamole, signs of toxicity among the survivors were ataxia and depression, while in those that died; prostration and tonic convulsions were also seen. After ASA, lethargy fluctuating with restlessness, bleeding through the nose and respiratory distress occurred. Some animals died in a prostrate position without any preceding agitation.
Symptomatology following administration of the combination dipyridamole/ASA, (1/5), did not differ appreciably from the toxic signs observed with either substance alone.
Subacute intravenous administration of dipyridamole to dogs at levels of 1 and 10 mg/kg/day for 4 weeks did not produce significant signs of toxicity. Oral dipyridamole (20, 40, 60, 80 mg/kg/day) administered for 13 weeks to beagles produced no toxic effect at the low dose but resulted in kidney toxicity with increasing doses. This was manifested by weight loss, increased blood urea and serum creatinine and epithelial nephritis at the high dose. The abnormalities were rapidly reversible upon discontinuation of treatment. When dogs were treated orally for 26 weeks with dipyridamole at doses of 10, 20 and 40 mg/kg/day, only occasional emesis occurred at the high dose level. Hematological, biochemical and urinary analyses were within normal limits. Rats fed dipyridamole in the diet at levels of 25, 75 and 225 mg/kg/day over a period of 27 weeks showed no signs of toxicity.
Treatment of rats for 3 months with the combination dipyridamole/ASA (1/5) at oral doses of 25, 100 and 400 mg/kg resulted in no drug-related toxicity except for a delay in body weight development in the high dose group. In chronic toxicity studies of 6 months duration in rats and dogs, dipyridamole/ASA (1/4) had no toxic effect at doses of 25 and 100 mg/kg in either species.
With increasing dose (200 and 400 mg/kg/day), renal and gastrointestinal lesions appeared along with associated biochemical changes. At the high dose in dogs, all animals were dead at 3 months. Control groups of dogs received ASA, 80 and 160 mg/kg/day. The lesions observed were similar to toxic signs in the combination treatment groups except for the nephritis and renal changes seen in the 200 and 400 mg/kg dose groups of dogs.
Two year carcinogenicity studies of dipyridamole in mouse and rat in doses up to 75 mg/kg demonstrated no tumorogenic effect of the drug. The dipyridamole/ASA combination (1/5) also produced no evidence of carcinogenicity in either rats or mice at oral doses up to 450 mg/kg. Mutagenicity assays (cytogenetic, microorganism, dominant lethal and micronucleus tests) of both dipyridamole alone and the dipyridamole/ASA combination (1/15) could not demonstrate any mutagenic potential of these compounds.
REFERENCES
- 1. Becker RM. The effect of platelet inhibition on platelet phenomena during cardiopulmonary bypass in pigs. Ann Roy CoIl Phys Surg (Can) 1973;180-90.
- 2. Beisenherz G, Koss FW, Schule A, Gebauer I, Barich R, and Frode R. Das schicksal des 2,6-bis(diäthanolamino)4,8 dipiperidino-pyrimido(5,4-d) pyrimidin im menschlichen und tierischen organismus. Arzneim-Forsch 1960; 10:307-12.
- 3. Blumenthal DS, Hutchins GM, Jugdutt BI, and Becker LC. Salvage of ischemic myocardium by dipyridamole in the conscious dog. Circulation 1981; 64: 915-23.
- 4. Born GVR, Mills DCB. Potentiation of the inhibitory effect of adenosine on platelet aggregation by drugs that prevent its uptake. Physiol Soc 1969; 202:4P.
- 5. Bouvier CA et al. Anomalies du compartement plaquettaire lors d’infartus du myocarde. Cardiologia 1967; 50: 232-8.
- 6. Buchanan MR, Rosenfeld J, Gent M, Lawrence W, Hirsh J. Increased dipyridamole plasma concentrations associated with salicylate administration. Relationship to effects on platelet aggregation in vivo. Thrombosis Res 1979; 15:813-20.
- 7. Chesebro JH, Clements IP, Fuster V, et al. A platelet-inhibitor-drug trial in coronary-artery bypass operations: benefit of perioperative dipyridamole and aspirin therapy on early post-operative vein-graft patency. N Engl J Med 1982; 307:73-8.
- 8. Chesebro JH, Fuster V, Elveback LR, et al. Effect of dipyridamole and aspirin on late vein-graft patency after coronary bypass operations. N Engl J Med 1984; 310:209-14.
- 9. Editorial. Platelet thrombosis on prosthetic valves. N Engl J Med 1968; 279:603-4.
- 10. Fam WM, McGregor M. The effect of coronary vasodilator drugs on retrograde flow in areas of chronic myocardial ischemia. Circulation Res 1964; 15: 355.
- 11. Fam WM, Ragheb S, Hoeschen RJ. Augmentation of intercoronary anastomosis by longterm administration of a vasodilator drug, dipyridamole (Persantin). Can Med Assoc J 1964; 90:970-3.
- 12. Feldman RL, Nichols WW, Pepine CJ, Conti CR. Acute effect of intravenous dipyridamole on regional coronary hemodynamics and metabolism. Circulation 1981; 64:333-44.
- 13. Flower RJ, Moncada S, Vane JR. Analgesic antipyretics and anti-inflammatory agents; drugs employed in the treatment of gout. pg. 693-695 in The Pharmacological Basis of Therapeutics, 6th ed (A.Goodman G, Goodman LS, Gilman A, eds.) Macmillan Co., New York 1980.
- 14. Fuster V, Dewanjee MK, Kaye MP, et al. Noninvasive radioisotopic technique for detection of platelet deposition in coronary artery bypass grafts in dogs and its reduction with platelet inhibitors. Circulation 1979; 60:1508-12.
- 15. Harker LA. Platelet kinetics and artificial heart valves. Clin Res 1970; 18:176 (abstr).
- 16. Harker LA, et al. Homocystinemia, vascular injury and arterial thrombosis. NEJM 1974; 291: 537-543.
- 17. Harker LA, Slichter SJ. Studies of platelet and fibrinogen kinetics in patients with prosthetic heart valves. N Engl J Med 1970; 283:1302-5.
- 18. Hasegawa T, et al. Prosthetic replacement of superior vena cava. Antiplatelet-adhesive drug influence. Arch Surg 1973; 106: 848.
- 19. Josa M, Lie JT, Bianco RL, Kaye MP. Reduction of thrombosis in canine coronary bypass vein grafts with dipyridamole and aspirin. Am J Cardiol 1981; 47:1248-54.
- 20. Kadatz R, Schroter HW, Weisenberger H. Persantin-darstellung der pharmakologischen, biochemischen und klinischen wirkung. Herz/Kreislauf 1973; 5:513-8.
- 21. Kadatz R, Schroter HW, Weisenberger H, Persantin-darstellung der pharmakologischen, biochemischen und klinischen wirkung (II). Herz/Kreislauf 1974; 6:21-31.
- 22. Mahony C, Wolfram KM, Bjornsson TD. Pharmacokinetics of dipyridamole in man. Clin Res 1980; 28: 240a (abstr).
- 23. Mellinger TJ, Bohorfoush JG. Pathways and tissue distribution of dipyridamole (Persantine). Arch Int Pharmacodyn 1965; 156: 380-8.
- 24. Metke MP, Lie JT, Fuster V, et al. Reduction of intimal thickening in canine coronary bypass vein grafts with dipyridamole and aspirin. Am J Cardiol 1979;43:1144-8.
- 25. Moncada S, Korbut R. Dipyridamole and other phosphodiesterase inhibitors act as antithrombotic agents by potentiating endogenous prostacyclin. Lancet 1978; 1: 1286-9.
- 26. Pedersen AK. Specific determination of dipyridamole in serum by high-performance liquid chromatography. J Chromatog 1979; 162:98-103.
- 27. Persantine-Aspirin Reinfarction Study Research Group. Persantine-aspirin reinfarction study. Design, methods and baseline results. Circulation 1980;62(Part II):111-142.
- 28. Persantine-Aspirin Reinfarction Study Research Group. Persantine and aspirin in coronary heart disease. Circulation 1980; 62 : 449-61.
- 29. Rajah SM, Crow MJ, Penny AF, Ahmad R, Watson DA. The effect of dipyridamole on platelet function: correlation with blood levels in man. Br J Clin Pharmac 1977; 4: 129-33.
- 30. Rajah SM, Penny AF, Crow MJ, Pepper MD, Watson DA. The interaction of varying doses of dipyridamole and acetylsalicylic acid on the inhibition of platelet functions and their effect on bleeding time. Br J Clin Pharmac 1979; 7:483-9.
- 31. Rees JR, Redding VJ. Increase in myocardial collateral capacity following drug-induced coronary vasodilatation. Am Heart J 1969; 78: 224-8.
- 32. Rosenfeld J, Buchanan MR, Reilly PA, Turpie AGG. Dipyridamole disposition after chronic administration: effect of aspirin. Thromb Res 1983;30(Suppl 19):137-43.
- 33. Rosner P, Berthoud S, Bouvier CA. In vitro effects of dipyridamole on platelet adhesiveness to glass. (a preliminary communication). Vox Sang. (Basel) 1967; 12: 300-4.
- 34. Roth GJ, Stanford N, Majerus PW. Proc Nat Acad Sci USA 1975; 72:3073.
- 35. Steele P, Rainwater J. Relationship of plasma anti-heparin activity and platelet survival time in coronary disease. Am Heart J 1980; 99: 438-42.
- 36. Steele P, Rainwater J, Vogel R. Effect of platelet suppressant treatment with dipyridamole and aspirin on exercise performance and platelet survival time in coronary disease. Chest 1981; 80: 557-61.
- 37. Sullivan JM, Harken DE, Gorlin R. Pharmacologic control of thromboembolic complications of cardiac-valve replacement. N Engl J Med 1968; 279: 576-80.
- 38. Sullivan JM, Harken DE, Gorlin R. Effect of dipyridamole on the incidence of arterial emboli after cardiac valve replacement. Circulation 1969; 40(Suppl 1): 149-153.
- 39. Sullivan JM, Harken DE, Gorlin R. Pharmacologic control of thromboembolic complications of cardiac-valve replacement. N Engl J Med 1971; 284: 1391-4.
- 40. Torres EC, Brandi G. The effect of vasoactive drugs on local coronary flow. Can J Physiol Pharmacol 1969;47:421-5.
- 41. Tyce GM, Fuster V, Owen CA. Dipyridamole levels in plasma of man and other species. Res Comm Chem Path Pharmacol 1979; 26:495-508.
- 42. Vineberg AM, Chari RS, Pifarre R, Mercier C. The effect of Persantin on intercoronary collateral circulation and survival during gradual experimental coronary occlusion. Can Med Assoc J 1962; 87: 336-45.
- 43. Weiss HJ, Aledort LM, Kochwa S. J Clin Invest 1968;47:2169.
- 44. Product Monograph, PERSANTINE, 50 mg and 75 mg tablets 5 mg/mL injectable ampoules, Boehringer Ingelheim Canada Ltd., Date of Revision: May 20, 2005, Control No: 092334.