


Product Monograph - Flolan
RECENT MAJOR LABEL CHANGES
| 7 WARNINGS AND PRECAUTIONS | 03/2024 |
|---|
TABLE OF CONTENTS
Sections or subsections that are not applicable at the time of authorization are not listed.
RECENT MAJOR LABEL CHANGES ............................................................................................. 2
TABLE OF CONTENTS ............................................................................................................... 2
PART I: HEALTH PROFESSIONAL INFORMATION ....................................................................... 4
1 INDICATIONS ................................................................................................................ 4
1.1 Pediatrics ................................................................................................................. 4
1.2 Geriatrics ................................................................................................................. 4
2 CONTRAINDICATIONS .................................................................................................. 4
4 DOSAGE AND ADMINISTRATION .................................................................................. 4
4.1 Dosing Considerations ............................................................................................. 4
4.2 Recommended Dose and Dosage Adjustment ........................................................ 5
4.3 Reconstitution ......................................................................................................... 6
4.4 Administration ......................................................................................................... 9
5 OVERDOSAGE ............................................................................................................... 9
6 DOSAGE FORMS, STRENGTHS, COMPOSITION AND PACKAGING ................................ 10
7 WARNINGS AND PRECAUTIONS ................................................................................. 10
7.1 Special Populations................................................................................................ 12
7.1.1 Pregnant Women ............................................................................................ 12
7.1.2 Breast-feeding ................................................................................................. 13
7.1.3 Pediatrics ......................................................................................................... 13
7.1.4 Geriatrics ......................................................................................................... 13
8 ADVERSE REACTIONS ................................................................................................. 13
8.2 Clinical Trial Adverse Reactions ............................................................................. 13
8.5 Post-Market Adverse Reactions ............................................................................ 21
9 DRUG INTERACTIONS ................................................................................................. 22
9.2 Drug Interactions Overview ................................................................................... 22
9.4 Drug-Drug Interactions .......................................................................................... 22
9.5 Drug-Food Interactions .......................................................................................... 22
9.6 Drug-Herb Interactions .......................................................................................... 22
9.7 Drug-Laboratory Test Interactions ......................................................................... 22
10 CLINICAL PHARMACOLOGY ........................................................................................ 23
10.1 Mechanism of Action ....................................................................................... 23
10.2 Pharmacodynamics ......................................................................................... 23
10.3 Pharmacokinetics ............................................................................................ 24
11 STORAGE, STABILITY AND DISPOSAL .......................................................................... 25
12 SPECIAL HANDLING INSTRUCTIONS ............................................................................ 26
PART II: SCIENTIFIC INFORMATION ........................................................................................ 26
13 PHARMACEUTICAL INFORMATION ............................................................................. 26
14 CLINICAL TRIALS ......................................................................................................... 27
14.1 Clinical Trials by Indication .............................................................................. 27
15 MICROBIOLOGY ......................................................................................................... 29
16 NON-CLINICAL TOXICOLOGY ...................................................................................... 29
PATIENT MEDICATION INFORMATION ................................................................................... 33
PART I: HEALTH PROFESSIONAL INFORMATION
1 INDICATIONS
FLOLAN (epoprostenol powder for injection) is indicated for the long-term intravenous treatment of idiopathic or heritable pulmonary arterial hypertension (PAH) or PAH associated with connective tissue diseases (CTD) in patients with WHO Functional Class III-IV symptoms who did not respond adequately to conventional therapy.
Prior to initiation of therapy, the potential benefit of FLOLAN should be weighed against the risks associated with use of the drug and the presence of an indwelling central venous catheter.
FLOLAN should be used only by clinicians experienced in the diagnosis and treatment of PAH. The diagnosis of idiopathic or heritable PAH or PAH/CTD should be carefully established by standard clinical tests.
1.1 Pediatrics
Pediatrics (< 18 years of age): No data are available to Health Canada; therefore, Health Canada has not authorized an indication for pediatric use.
1.2 Geriatrics
Geriatrics (≥65 years of age): Clinical studies of FLOLAN did not include sufficient numbers of patients aged 65 and over to determine whether they respond differently from younger patients. In general, dose selection for an elderly patient should be made carefully, reflecting the greater frequency of decreased hepatic, renal, or cardiac function and of concomitant disease or other drug therapy.
2 CONTRAINDICATIONS
- FLOLAN is contraindicated in patients with known or suspected hypersensitivity to the drug or any of its excipients, to structurally-related compounds, or component of the container. For a complete listing, see 6 DOSAGE FORMS, STRENGTHS, COMPOSITION AND PACKAGING.
- The chronic use of FLOLAN in patients with congestive heart failure (CHF) due to severe left ventricular systolic dysfunction is contraindicated. A large study evaluating the effect of FLOLAN on survival in NYHA Class III and IV patients with CHF due to severe left ventricular systolic dysfunction was terminated after an interim analysis of 471 patients revealed a higher mortality in patients receiving FLOLAN plus conventional therapy than in those receiving conventional therapy alone.
- FLOLAN should not be used chronically in patients who develop pulmonary edema during dose initiation (see Pulmonary Edema).
4 DOSAGE AND ADMINISTRATION
4.1 Dosing Considerations
FLOLAN is not to be used for bolus administration. FLOLAN is only indicated for continuous intravenous infusion.
During acute dose-ranging, asymptomatic increases in pulmonary artery pressure coincident with increases in cardiac output occurred rarely. In such cases, dose reduction should be considered, but such an increase does not imply that chronic treatment is contraindicated. However, in the rare occurrence of pulmonary edema, chronic treatment is contraindicated.
During chronic use, FLOLAN is delivered continuously on an ambulatory basis through a permanent indwelling central venous catheter. Unless contraindicated, anticoagulant therapy should be administered to patients with idiopathic or heritable PAH receiving FLOLAN to reduce the risk of pulmonary thromboembolism or systemic embolism through a patent foramen ovale. In order to reduce the risk of infection, aseptic technique must be used in the reconstitution and administration of FLOLAN as well as in routine catheter care. Because FLOLAN is metabolized rapidly, even brief interruptions in the delivery of FLOLAN may result in symptoms associated with rebound PAH including dyspnea, dizziness, and asthenia. The decision to initiate therapy with FLOLAN should be based upon the understanding that there is a high likelihood that intravenous therapy with FLOLAN will be needed for prolonged periods, possibly years, and the patient's ability to accept and care for a permanent intravenous catheter and infusion pump should be carefully considered.
FLOLAN can be used in acute vasoreactivity studies, to assess pulmonary vasodilator capacity.
4.2 Recommended Dose and Dosage Adjustment
Initial Dosage
Chronic infusion of FLOLAN should be initiated at 2 ng/kg/min and increased until dose-limiting pharmacological effects are elicited or until a tolerance limit to the drug is established and further increases in the infusion rate are not clinically warranted (see Dosage Adjustments below). If dose-limiting pharmacologic effects occur, the infusion rate should be decreased to an appropriate chronic infusion rate whereby the pharmacologic effects of FLOLAN are tolerated. In clinical trials, the most common dose-limiting adverse events were nausea, vomiting, hypotension, sepsis, headache, abdominal pain, or respiratory disorder (most treatment limiting adverse events were not serious). If the initial infusion rate of 2 ng/kg per minute is not tolerated, a lower dose which is tolerated by the patient should be identified.
In the controlled 12-week trial in PAH associated with Scleroderma Spectrum of Diseases (PAH/SSD), for example, the dose increased from a mean starting dose of 2.2 ng/kg/min. During the first seven days of treatment, the dose was increased daily to a mean dose of 4.1 ng/kg/min on day 7 of treatment. At the end of week 12, the mean dose was 11.2 ng/kg/min. The mean incremental increase was 2 to 3 ng/kg/min every 3 weeks.
Dosage Adjustments
Changes in the chronic infusion rate should be based on persistence, recurrence or worsening of the patient's symptoms of PAH and the occurrence of adverse events due to excessive doses of FLOLAN. In general, the need for increases in dose from the initial chronic dose should be expected over time.
Incremental increases in dose should be considered if symptoms of PAH persist or recur after improving. The infusion should be increased by 1 to 2 ng/kg/min increments at intervals sufficient to allow assessment of clinical response and tolerability; these intervals should be of at least 15 minutes. Following establishment of a new chronic infusion rate, the patient should be observed, and standing and supine blood pressure and heart rate monitored for several hours to ensure that the new dose is tolerated.
During chronic infusion, the occurrence of dose-limiting pharmacologic events may necessitate a decrease in infusion rate, but the adverse event may occasionally resolve without dosage adjustment. Dosage decreases should generally be made gradually in 2 ng/kg/min decrements every 15 minutes or longer until the dose-limiting effects resolve. Abrupt withdrawal of FLOLAN or sudden large reductions in infusion rates should be avoided. Except in life-threatening situations (e.g. unconsciousness, collapse, etc.), infusion rates of FLOLAN should be adjusted only under the direction of a physician (see General).
In patients receiving lung transplants, doses of FLOLAN were tapered after the initiation of cardiopulmonary bypass.
4.3 Reconstitution
The diluent and reconstituted solution should be inspected visually for any particulate matter and/or abnormal physical appearance. In the event of either being observed, the diluent or reconstituted solution should be discarded.
FLOLAN IS ONLY STABLE WHEN RECONSTITUTED WITH pH 12 STERILE DILUENT for FLOLAN. FLOLAN MUST NOT BE RECONSTITUTED OR MIXED WITH ANY OTHER PARENTERAL MEDICATIONS OR SOLUTIONS PRIOR TO OR DURING ADMINISTRATION.
FLOLAN solution prepared with pH 12 STERILE DILUENT for FLOLAN must not be used with any preparation or administration material containing polyethylene terephthalate (PET) or polyethylene terephthalate glycol (PETG). Physicians should ensure patients receive appropriate supplies if they self-administer FLOLAN, and patients should be directed to only use FLOLAN with the supplies provided.
A concentration for the solution of FLOLAN should be selected that is compatible with the infusion pump being used with respect to minimum and maximum flow rates, reservoir capacity, and the infusion pump criteria listed above. FLOLAN, when administered chronically, should be prepared in a drug delivery reservoir appropriate for the infusion pump with a total reservoir volume of at least 100 mL. FLOLAN should be prepared using 2 vials of pH 12 STERILE DILUENT for FLOLAN. Each vial is for single use only; discard any unused solution.
Table 1 gives directions for preparing several different concentrations of FLOLAN.
Table 1 - Reconstitution and Dilution Instructions using pH 12 STERILE DILUENT for FLOLAN
| Directions | To make 100 mL of Solution with Final Concentration (ng/mL) of: |
|---|---|
| Dissolve contents of one 0.5 mg vial with 5 mL of pH 12 STERILE DILUENT for FLOLAN. Withdraw 3 mL and add to sufficient pH 12 STERILE DILUENT for FLOLAN to make a total of 100 mL. | 3,000 ng/mL |
| Dissolve contents of one 0.5 mg vial with 5 mL of pH 12 STERILE DILUENT for FLOLAN. Withdraw entire vial contents and add sufficient pH 12 STERILE DILUENT for FLOLAN to make a total of 100 mL. | 5,000 ng/mL |
| Dissolve contents of two 0.5 mg vials each with 5 mL of pH 12 STERILE DILUENT for FLOLAN. Withdraw entire vial contents and add sufficient pH 12 STERILE DILUENT for FLOLAN to make a total of 100 mL. | 10,000 ng/mL |
| Directions | To make 100 mL of Solution with Final Concentration (ng/mL) of: |
|---|---|
| Dissolve contents of one 1.5 mg vial with 5 mL of pH 12 STERILE DILUENT for FLOLAN. Withdraw entire vial contents and add sufficient pH 12 STERILE DILUENT for FLOLAN to make a total of 100 mL. | 15,000 ng/mL |
Particular care should be taken in the preparation of the infusion and in calculating the rate of infusion. The procedures given below should be closely followed.
Infusion Rates During Acute Dose Escalation
Generally, 3,000 ng/mL and 10,000 ng/mL are satisfactory concentrations to deliver between 2 to 16 ng/kg/min in adults. Infusion rates may be calculated using the following formula:
[Dose (ng/kg/min) x Weight (kg) x 60 min/hr]
Infusion Rate (mL/hr) = _____________________________________________
Final Concentration (ng/mL)
Tables 2 through 5 provide infusion rates for doses up to 16 ng/kg/min based upon patient weight, drug delivery rate, and concentration of the solution of FLOLAN to be used. These tables may be used to select the most appropriate concentration of FLOLAN that will result in an infusion rate between the minimum and maximum flow rates of the infusion pump and which will allow the desired duration of infusion from a given reservoir volume.
Table 2 - Infusion Rates for FLOLAN at a Concentration of 3,000 ng/mL
| Dose or Drug Delivery Rate (ng/kg/min) | |||||||||||||||||||
|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|
Patient Weight (kg) | 2 | 4 | 6 | 8 | 10 | 12 | 14 | 16 | |||||||||||
| Infusion Delivery Rate (mL/hr) | |||||||||||||||||||
| 10 | - | - | 1.2 | 1.6 | 2.0 | 2.4 | 2.8 | 3.2 | |||||||||||
| 20 | - | 1.6 | 2.4 | 3.2 | 4.0 | 4.8 | 5.6 | 6.4 | |||||||||||
| 30 | 1.2 | 2.4 | 3.6 | 4.8 | 6.0 | 7.2 | 8.4 | 9.6 | |||||||||||
| 40 | 1.6 | 3.2 | 4.8 | 6.4 | 8.0 | 9.6 | 11.2 | 12.8 | |||||||||||
| 50 | 2.0 | 4.0 | 6.0 | 8.0 | 10.0 | 12.0 | 14.0 | 16.0 | |||||||||||
| 60 | 2.4 | 4.8 | 7.2 | 9.6 | 12.0 | 14.4 | 16.8 | 19.2 | |||||||||||
| 70 | 2.8 | 5.6 | 8.4 | 11.2 | 14.0 | 16.8 | 19.6 | 22.4 | |||||||||||
| 80 | 3.2 | 6.4 | 9.6 | 12.8 | 16.0 | 19.2 | 22.4 | 25.6 | |||||||||||
| 90 | 3.6 | 7.2 | 10.8 | 14.4 | 18.0 | 21.6 | 25.2 | 28.8 | |||||||||||
| 100 | 4.0 | 8.0 | 12.0 | 16.0 | 20.0 | 24.0 | 28.0 | 32.0 | |||||||||||
Table 3 - Infusion Rates for FLOLAN at a Concentration of 5,000 ng/mL
| Dose or Drug Delivery Rate (ng/kg/min) | |||||||||||||||||||
|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|
Patient Weight (kg) | 2 | 4 | 6 | 8 | 10 | 12 | 14 | 16 | |||||||||||
| Infusion Delivery Rate (mL/hr) | |||||||||||||||||||
| 10 | - | - | - | 1.0 | 1.2 | 1.4 | 1.7 | 1.9 | |||||||||||
| 20 | - | 1.0 | 1.4 | 1.9 | 2.4 | 2.9 | 3.4 | 3.8 | |||||||||||
| 30 | - | 1.4 | 2.2 | 2.9 | 3.6 | 4.3 | 5.0 | 5.8 | |||||||||||
| 40 | 1.0 | 1.9 | 2.9 | 3.8 | 4.8 | 5.8 | 6.7 | 7.7 | |||||||||||
| 50 | 1.2 | 2.4 | 3.6 | 4.8 | 6.0 | 7.2 | 8.4 | 9.6 | |||||||||||
| 60 | 1.4 | 2.9 | 4.3 | 5.8 | 7.2 | 8.6 | 10.1 | 11.5 | |||||||||||
| 70 | 1.7 | 3.4 | 5.0 | 6.7 | 8.4 | 10.1 | 11.8 | 13.4 | |||||||||||
| 80 | 1.9 | 3.8 | 5.8 | 7.7 | 9.6 | 11.5 | 13.4 | 15.4 | |||||||||||
| 90 | 2.2 | 4.3 | 6.5 | 8.6 | 10.8 | 13.0 | 15.1 | 17.3 | |||||||||||
| 100 | 2.4 | 4.8 | 7.2 | 9.6 | 12.0 | 14.4 | 16.8 | 19.2 | |||||||||||
Table 4 - Infusion Rates for FLOLAN at a Concentration of 10,000 ng/mL
| Dose or Drug Delivery Rate (ng/kg/min) | |||||||||||||
|---|---|---|---|---|---|---|---|---|---|---|---|---|---|
Patient Weight (kg) | 4 | 6 | 8 | 10 | 12 | 14 | 16 | ||||||
| Infusion Delivery Rate (mL/hr) | |||||||||||||
| 20 | - | - | 1.0 | 1.2 | 1.4 | 1.7 | 1.9 | ||||||
| 30 | - | 1.1 | 1.4 | 1.8 | 2.2 | 2.5 | 2.9 | ||||||
| 40 | 1.0 | 1.4 | 1.9 | 2.4 | 2.9 | 3.4 | 3.8 | ||||||
| 50 | 1.2 | 1.8 | 2.4 | 3.0 | 3.6 | 4.2 | 4.8 | ||||||
| 60 | 1.4 | 2.2 | 2.9 | 3.6 | 4.3 | 5.0 | 5.8 | ||||||
| 70 | 1.7 | 2.5 | 3.4 | 4.2 | 5.0 | 5.9 | 6.7 | ||||||
| 80 | 1.9 | 2.9 | 3.8 | 4.8 | 5.8 | 6.7 | 7.7 | ||||||
| 90 | 2.2 | 3.2 | 4.3 | 5.4 | 6.5 | 7.6 | 8.6 | ||||||
| 100 | 2.4 | 3.6 | 4.8 | 6.0 | 7.2 | 8.4 | 9.6 | ||||||
Table 5 - Infusion Rates for FLOLAN at a Concentration of 15,000 ng/mL
| Dose or Drug Delivery Rate (ng/kg/min) | |||||||||||||
|---|---|---|---|---|---|---|---|---|---|---|---|---|---|
Patient Weight (kg) | 4 | 6 | 8 | 10 | 12 | 14 | 16 | ||||||
| Infusion Delivery Rate (mL/hr) | |||||||||||||
| 30 | - | - | 1.0 | 1.2 | 1.4 | 1.7 | 1.9 | ||||||
| 40 | - | 1.0 | 1.3 | 1.6 | 1.9 | 2.2 | 2.6 | ||||||
| 50 | - | 1.2 | 1.6 | 2.0 | 2.4 | 2.8 | 3.2 | ||||||
| 60 | 1.0 | 1.4 | 1.9 | 2.4 | 2.9 | 3.4 | 3.8 | ||||||
| 70 | 1.1 | 1.7 | 2.2 | 2.8 | 3.4 | 3.9 | 4.5 | ||||||
| 80 | 1.3 | 1.9 | 2.6 | 3.2 | 3.8 | 4.5 | 5.1 | ||||||
| 90 | 1.4 | 2.2 | 2.9 | 3.6 | 4.3 | 5.0 | 5.8 | ||||||
| 100 | 1.6 | 2.4 | 3.2 | 4.0 | 4.8 | 5.6 | 6.4 | ||||||
Infusion Rates During Chronic Infusion
More concentrated solutions than those described in the above tables may be necessary in some cases where higher drug delivery rates are indicated. Generally, over time the daily dose of FLOLAN requires up-titration.
4.4 Administration
FLOLAN must be reconstituted only with pH 12 STERILE DILUENT for FLOLAN to maintain the pH. The stability of solutions of FLOLAN is pH dependent.
Reconstituted solutions prepared with pH 12 STERILE DILUENT for FLOLAN do NOT require use with a cold pouch during administration (see 11 STORAGE, STABILITY and DISPOSAL). Reconstituted solutions of FLOLAN must not be diluted or administered with other parenteral solutions or medications (see 7 WARNINGS AND PRECAUTIONS).
Continuous chronic infusion of FLOLAN should be administered through a central venous catheter using an ambulatory infusion pump as recommended by the physician. Temporary peripheral intravenous infusion may be used until central access is established.
The ambulatory infusion pump used to administer FLOLAN should:
- 1) be small and lightweight,
- 2) be able to adjust infusion rates in 2 ng/kg/min increments,
- 3) have occlusion, end of infusion, and low battery alarms,
- 4) be accurate to ±6% of the programmed rate,
- 5) be positive pressure driven (continuous or pulsatile) with intervals between pulses not exceeding 3 minutes at infusion rates used to deliver FLOLAN,
- 6) have design characteristics that minimize the likelihood of accidental bolus administration.
The reservoir should be made of polyvinyl chloride, or polypropylene, or glass. The infusion pump used in the most recent clinical trials was the CADD-1 HFX 5100 (SIMS Deltec). A 60" microbore non-DEHP extension set with proximal antisyphon valve, low priming volume (0.9 mL), CADD disposable Medication Cassette Reservoir 100 mL, and in-line 0.22 micron filter was used during clinical trials. The final infusion solution must be filtered with a sterile 0.22 micron or 0.20 micron filter prior to, or during administration.
To avoid potential interruptions in drug delivery, the patient should have access to a back-up infusion pump and additional intravenous infusion sets. A multi-lumen catheter should be considered if other intravenous therapies are routinely administered.
Preliminary data suggest that peristaltic pumps may have advantages over syringe pumps.
5 OVERDOSAGE
Signs and symptoms of excessive doses of FLOLAN are the expected dose-limiting pharmacologic effects of FLOLAN including flushing, headache, hypotension and complications of hypotension (e.g. tachycardia, nausea, vomiting, and diarrhea). Treatment will ordinarily require dose reduction of FLOLAN or discontinue the infusion and initiate appropriate supportive measures as necessary; for example plasma volume expansion and/or adjustment to pump flow.
One patient with PAH/CTD accidentally received 50 mL of an unspecified concentration of FLOLAN. The patient vomited and became unconscious with an initially unobtainable blood pressure. FLOLAN was discontinued and the patient regained consciousness within seconds.
| For management of a suspected drug overdose, contact your regional poison control centre. |
|---|
6 DOSAGE FORMS, STRENGTHS, COMPOSITION AND PACKAGING
Table 6 - Dosage Forms, Strengths, Composition and Packaging
FLOLAN is supplied as a sterile freeze-dried powder in flint glass vials with synthetic gray butyl rubber closures and aluminum collars with a flip-top cover, individually packaged in a carton.
pH 12 STERILE DILUENT for FLOLAN is supplied in plastic vials containing 50 mL diluent with fluororesin faced bromobutyl rubber closures with aluminum overseal and lavender plastic flip-off cap, tray of 2.
FLOLAN is supplied as a vial containing a white or off-white freeze-dried powder.
pH 12 STERILE DILUENT for FLOLAN is supplied in plastic vials containing 50 mL diluent, a clear colourless solution to reconstitute freeze-dried powder.
7 WARNINGS AND PRECAUTIONS
General
FLOLAN must be reconstituted only as directed using pH 12 STERILE DILUENT for FLOLAN. FLOLAN must not be reconstituted or mixed with any other parenteral medications or solutions prior to or during administration.
FLOLAN is not to be used for bolus administration (see Adverse Events During Dose Escalation).
The sterile diluent contains no preservative; consequently a vial should be used once only and then discarded.
Because of the high pH of the final infusion solutions, care should be taken to avoid extravasation during their administration and consequent risk of tissue damage.
During the early phase of chronic administration, intense patient education is required.
| Route of Administration | Dosage Form / Strength/Composition | Non-medicinal Ingredients |
| Intravenous | FLOLAN Powder for Injection Vials:
| FLOLAN Powder for Injection: glycine, mannitol, sodium chloride, and sodium hydroxide pH 12 STERILE DILUENT for FLOLAN (pH 11.7-12.3): glycine, sodium chloride, sodium hydroxide, and water for injection |
Due to the potential for problems associated with the drug delivery system, immediate access to medical care should be available during chronic treatment.
Abrupt Withdrawal: Abrupt withdrawal (including interruptions in drug delivery) or sudden large reductions in dosage of FLOLAN may result in symptoms associated with rebound PAH, including dyspnea, dizziness, and asthenia and may lead to death. In clinical trials, there were rare reports of deaths considered attributable to the interruption of FLOLAN. Abrupt withdrawal should be avoided, except in life-threatening situations (e.g. unconsciousness, collapse, etc).
Dose Initiation: FLOLAN is a potent pulmonary and systemic vasodilator. The cardiovascular effects during infusion disappear within 30 minutes of the end of administration. Acute dose initiation with FLOLAN must be performed in a hospital setting with adequate personnel and equipment for physiologic monitoring and emergency care.
Chronic Use and Dose Adjustment: FLOLAN is infused continuously through a permanent indwelling central venous catheter via a small, portable infusion pump. Thus, therapy with FLOLAN requires commitment by the patient to drug reconstitution, drug administration, care of the permanent central venous catheter, and access to intense and ongoing patient education. Sterile technique must be adhered to in preparing the drug and in the care of the catheter, and even brief interruptions in the delivery of FLOLAN may result in rapid symptomatic deterioration. The decision to receive FLOLAN for PAH should be based upon the understanding that there is a high likelihood that therapy with FLOLAN will be needed for prolonged periods, possibly years, and the patient's ability to accept and care for a permanent intravenous catheter and infusion pump should be carefully considered.
Based on clinical trials, the acute hemodynamic response to FLOLAN did not correlate well with survival during chronic use of FLOLAN. Dosage of FLOLAN during chronic use should be adjusted at the first sign of recurrence or worsening of symptoms attributable to PAH, or the occurrence of adverse events associated with FLOLAN (see 4 DOSAGE AND ADMINISTRATION). During administration and following dosage adjustments, standing and supine blood pressure and heart rate should be monitored closely for several hours.
Cardiovascular
FLOLAN use has been associated with an increased incidence of bradycardia in patients with PAH and with episodes of severe hypotension, including fatalities.
If excessive hypotension occurs during administration of FLOLAN the dose should be reduced or the infusion discontinued. Hypotension may be profound in overdose and may result in loss of consciousness (see 5 OVERDOSAGE).
During ongoing treatment, patients should avoid situations which promote vasodilation such as saunas, hot baths and sunbathing. Severe hypotension has been seen in patients treated with chronic FLOLAN infusions under such circumstances.
Driving and Operating Machinery
PAH and its therapeutic management may affect the ability to drive and operate machinery. Exercise caution when driving or operating a vehicle or potentially dangerous machinery.
Endocrine and Metabolism
Elevated serum glucose levels have been reported.
Gastrointestinal
Post-marketing cases of ascites have been reported in patients using epoprostenol. The majority of cases have occurred in patients with risk factors such as right heart failure or chronic congestive hepatopathy. However, in cases where ascites is not attributable to other causes, clinicians should consider dose reduction or discontinuation of FLOLAN therapy.
Hematologic
Epoprostenol is a potent inhibitor of platelet aggregation, therefore, an increased risk for hemorrhagic complications should be considered, particularly for patients with other risk factors for bleeding (see Monitoring and Laboratory Tests and 9 DRUG INTERACTIONS).
Monitoring and Laboratory Tests
Prothrombin times should be monitored because anticoagulant therapy is generally recommended in these patients. Platelet counts should also be monitored.
Peri-Operative Considerations
Sepsis/septicemia is a known risk associated with the presence of an indwelling central venous catheter and requires immediate access to expert medical care (see Adverse Events Associated with the Drug Delivery System).
Reproductive Health: Female and Male Potential
Fertility
Animal studies did not indicate harmful effects with respect to fertility. However, the relevance of these findings in humans is unknown (see 16 NON-CLINICAL TOXICOLOGY).
Respiratory
Pulmonary Edema
A minority of patients have PAH associated with pulmonary veno-occlusive disease. Some of these patients develop pulmonary edema during dose initiation. Where pulmonary edema arises within hours to days of starting FLOLAN infusion, a diagnosis of veno-occlusive disease should be considered. In such cases consideration should be given to discontinuation of FLOLAN. FLOLAN should be discontinued after dose tapering.
FLOLAN should not be used chronically in patients who develop pulmonary edema during dose initiation.
7.1 Special Populations
7.1.1 Pregnant Women
There are no adequate and well-controlled studies in pregnant women. Animal studies did not indicate harmful effects with respect to pregnancy, embryonal/fetal development, parturition or postnatal development. However, the relevance of these findings in humans is unknown (see 16 NON-CLINICAL TOXICOLOGY).
The use of FLOLAN during labor, vaginal delivery, or caesarean section has not been studied in humans.
7.1.2 Breast-feeding
It is not known whether epoprostenol or its metabolites are excreted in human milk. A risk to the nursing child cannot be excluded. Because many drugs are excreted in human milk, consideration should be given to discontinuation of breast feeding when FLOLAN is to be administered to a nursing woman or to discontinue/abstain from epoprostenol therapy taking into account the benefit of breast feeding for the child and the benefit of therapy for the woman.
7.1.3 Pediatrics
Pediatrics: No data are available to Health Canada; therefore, Health Canada has not authorized an indication for pediatric use.
7.1.4 Geriatrics
Geriatrics (≥65 years of age): Clinical studies of FLOLAN did not include sufficient numbers of patients aged 65 and over to determine whether they respond differently from younger patients. In general, dose selection for an elderly patient should be made carefully, reflecting the greater frequency of decreased hepatic, renal, or cardiac function and of concomitant disease or other drug therapy.
8 ADVERSE REACTIONS
8.2 Clinical Trial Adverse Reactions
Clinical trials are conducted under very specific conditions. The adverse reaction rates observed in the clinical trials; therefore, may not reflect the rates observed in practice and should not be compared to the rates in the clinical trials of another drug. Adverse reaction information from clinical trials may be useful in identifying and approximating rates of adverse drug reactions in real-world use.
During clinical trials, adverse events were classified as follows: (1) adverse events during dose escalation, (2) adverse events during chronic administration, and (3) adverse events associated with the drug delivery system.
Adverse Events During Dose Escalation
In early clinical trials, FLOLAN was increased in 2 ng/kg/min increments until such time as the patients developed symptomatic intolerance. The most common adverse events and those that limited further increases in dose were generally related to the major pharmacologic effect of FLOLAN, i.e. vasodilation.
Table 7 lists the adverse events reported during dose escalation in decreasing order of frequency as well as the percent of cases where the event was dose limiting. Age related differences (< 16 vs ≥16 years) in the incidence of adverse events are shown in Table 8.
Table 7 - Adverse Events During Dose Escalation
Adverse Events Occurring in ≥ 1% of patients | FLOLAN (n=391) % of patients where event was reported | FLOLAN (n=391) % of patients where event was dose-limiting |
|---|---|---|
| Flushing | 58 | 14 |
| Headache | 49 | 18 |
| Nausea/Vomiting | 32 | 19 |
| Hypotension | 16 | 15 |
| Anxiety, nervousness, agitation | 11 | 7 |
| Chest pain | 11 | 7 |
| Dizziness | 8 | 4 |
| Bradycardia | 5 | 4 |
| Abdominal pain | 5 | 2 |
| Musculoskeletal pain | 3 | 2 |
| Dyspnea | 2 | 2 |
| Back pain | 2 | - |
| Sweating | 1 | ≤ 1 |
| Dyspepsia | 1 | ≤ 1 |
| Hypesthesia/Paresthesia | 1 | ≤ 1 |
| Tachycardia | 1 | ≤ 1 |
Table 8 - Age Related Adverse Events During Dose Escalation
Adverse Events
< 16 years (n=63) % of patients reporting event | ≥ 16 years (n=328) % of patients reporting event | |
|---|---|---|
| Flushing | 14 | 66 |
| Headache | 8 | 57 |
| Nausea/Vomiting | 40 | 30 |
| Hypotension | 14 | 16 |
| Anxiety, nervousness, agitation | 21 | 9 |
| Chest pain | 0 | 13 |
| Dizziness | 2 | 9 |
| Bradycardia | 6 | 5 |
| Abdominal pain | 6 | 5 |
Adverse Events During Chronic Administration
Interpretation of adverse events is complicated by the clinical features of PAH, which may be similar to some of the pharmacologic effects of FLOLAN (e.g. dizziness, syncope). Adverse events probably related to the underlying disease include dyspnea, fatigue, chest pain, edema, hypoxia, right ventricular failure and pallor. Several adverse events, on the other hand, can clearly be attributed to FLOLAN. These include jaw pain, flushing, headache, diarrhea, nausea and vomiting, flu-like symptoms, and anxiety/nervousness.
Adverse Events During Chronic Administration for Idiopathic or Heritable PAH
In an effort to separate the adverse effects of the drug from the adverse effects of the underlying disease, Table 9 lists adverse events that occurred at a rate at least 10% different in the two groups in controlled trials for idiopathic or heritable PAH.
Table 9 - Adverse Events Regardless of Attribution Occurring in Patients with Idiopathic or Heritable PAH During Chronic Administration in Controlled Trials with Greater than or Equal to 10 Percent Difference between FLOLAN and Conventional Therapy Alone
| Adverse Event | FLOLAN (n=52) % of patients | Conventional Therapya (n=54) % of patients |
|---|---|---|
| Occurrence More Common with FLOLAN | ||
| General | ||
| Chills/Fever/Sepsis/Flu-like symptoms | 25 | 11 |
| Cardiovascular | ||
| Tachycardia | 35 | 24 |
| Flushing | 42 | 2 |
| Gastrointestinal | ||
| Diarrhea | 37 | 6 |
| Nausea/Vomiting | 67 | 48 |
| Musculoskeletal | ||
| Jaw Pain | 54 | 0 |
| Myalgia | 44 | 31 |
| Non-specific musculoskeletal pain | 35 | 15 |
| Neurological | ||
| Anxiety/nervousness/tremor | 21 | 9 |
| Dizziness | 83 | 70 |
| Headache | 83 | 33 |
| Hypesthesia, Hyperesthesia, Paresthesia | 12 | 2 |
| Occurrence More Common with Conventional Therapy | ||
| Cardiovascular | ||
| Heart Failure | 31 | 52 |
| Syncope | 13 | 24 |
| Shock | 0 | 13 |
| Respiratory | ||
| Hypoxia | 25 | 37 |
a Conventional therapy varied among patients and included some or all of the following: anticoagulants, supplemental oxygen, diuretics, oral vasodilators, and digoxin.
Thrombocytopenia, dry mouth, lassitude, chest tightness and bleeding at various sites (e.g. pulmonary, gastrointestinal, epistaxis, intracranial, post-procedural, retroperitoneal) have been reported during uncontrolled clinical trials and post marketing clinical use in patients receiving FLOLAN.
Table 10 lists those additional adverse events reported in patients with idiopathic or heritable PAH receiving FLOLAN plus conventional therapy versus conventional therapy alone during controlled clinical trials where the difference in incidence of the event between treatment groups was < 10%.
Table 10 - Adverse Events Regardless of Attribution Occurring During Chronic Administration in Controlled Trials with Less than 10 Percent Difference between FLOLAN and Conventional Therapy Alone
| Adverse Event | FLOLAN (n=52) % of patients | Conventional Therapy (n=54) % of patients |
|---|---|---|
| GENERAL | ||
| Asthenia | 87 | 81 |
| CARDIOVASCULAR | ||
| Angina Pectoris | 19 | 20 |
| Arrhythmia | 27 | 20 |
| Bradycardia | 15 | 9 |
| Supraventricular tachycardia | 8 | 0 |
| Pallor | 21 | 30 |
| Cyanosis | 31 | 39 |
| Palpitation | 63 | 61 |
| Cerebrovascular accident | 4 | 0 |
| Hypotension | 27 | 31 |
| Myocardial ischemia | 2 | 6 |
| GASTROINTESTINAL | ||
| Abdominal pain | 27 | 31 |
| Anorexia | 25 | 30 |
| Ascites | 12 | 17 |
| Constipation | 6 | 2 |
| METABOLIC | ||
| Edema | 60 | 63 |
| Hypokalemia | 6 | 4 |
| Weight reduction | 27 | 24 |
| Weight gain | 6 | 4 |
| MUSCULOSKELETAL | ||
| Arthralgia | 6 | 0 |
| Bone pain | 0 | 4 |
| Chest pain | 67 | 65 |
| NEUROLOGICAL | ||
| Confusion | 6 | 11 |
| Convulsion | 4 | 0 |
| Depression | 37 | 44 |
| Insomnia | 4 | 4 |
| RESPIRATORY | ||
| Cough increase | 38 | 46 |
| Dyspnea | 90 | 85 |
| Epistaxis | 4 | 2 |
| Adverse Event | FLOLAN (n=52) % of patients | Conventional Therapy (n=54) % of patients |
|---|---|---|
| Pleural effusion | 4 | 2 |
| SKIN AND APPENDAGES | ||
| Pruritus | 4 | 0 |
| Rash | 10 | 13 |
| Sweating | 15 | 20 |
| SPECIAL SENSES | ||
| Amblyopia | 8 | 4 |
| Vision abnormality | 4 | 0 |
| OTHER | ||
| Hemorrhage | 19 | 11 |
Although the number of patients was small, in controlled trials there was a trend towards increased incidence of bradycardia associated with chronic treatment in patients < 16 vs those ≥ 16 years of age. Bradycardia, sometimes accompanied by orthostatic hypotension, has occurred in healthy volunteers at doses of epoprostenol greater than 5 ng/kg/min. Bradycardia associated with a considerable fall in systolic and diastolic blood pressure has followed i.v. administration of a dose of epoprostenol equivalent to 30 ng/kg/min in healthy conscious volunteers.
Adverse Events During Chronic Administration for PAH/SSD
In an effort to separate the adverse effects of the drug from the adverse effects of the underlying disease, Table 11 lists adverse events that occurred at a rate at least 10% different between the two groups in the controlled trial for patients with PAH/SSD.
Table 11 - Adverse Events Regardless of Attribution Occurring in Patients with PAH/SSD with Greater than or Equal to 10 Percent Difference between FLOLAN and Conventional Therapy Alone
| Adverse Event | FLOLAN % n = 56 | Conventional Therapy % n = 55 |
|---|---|---|
| Occurrence More Common with FLOLAN | ||
| CARDIOVASCULAR | ||
| Flushing | 23 | 0 |
| Hypotension | 13 | 0 |
| GASTROINTESTINAL | ||
| Anorexia | 66 | 47 |
| Nausea/vomiting | 41 | 16 |
| Diarrhea | 50 | 5 |
| MUSCULOSKELETAL | ||
| Jaw pain | 75 | 0 |
| Pain/neck pain/arthralgia | 84 | 65 |
| Adverse Event | FLOLAN % n = 56 | Conventional Therapy % n = 55 |
|---|---|---|
| NEUROLOGICAL | ||
| Headache | 46 | 5 |
| SKIN AND APPENDAGES | ||
| Skin ulcer | 39 | 24 |
| Eczema/rash/urticaria | 25 | 4 |
| Occurrence More Common with Conventional Therapy | ||
| CARDIOVASCULAR | ||
| Cyanosis | 54 | 80 |
| Pallor | 32 | 53 |
| Syncope | 7 | 20 |
| GASTROINTESTINAL | ||
| Ascites | 23 | 33 |
| Esophageal reflux/gastritis | 61 | 73 |
| METABOLIC | ||
| Weight decrease | 45 | 56 |
| NEUROLOGICAL | ||
| Dizziness | 59 | 76 |
| RESPIRATORY | ||
| Hypoxia | 55 | 65 |
Table 12 lists additional adverse events reported in PAH/SSD patients receiving FLOLAN plus conventional therapy or conventional therapy alone during controlled clinical trials.
Table 12 - Adverse Events Regardless of Attribution Occurring in Patients with PAH/SSD with Less than 10 Percent Difference Between FLOLAN and Conventional Therapy Alone
| Adverse Event* | FLOLAN % n = 56 | Conventional Therapy % n = 55 |
|---|---|---|
| GENERAL | ||
| Asthenia | 100 | 98 |
| Hemorrhage/hemorrhage injection | 11 | 2 |
| Site/hemorrhage rectal | ||
| Infection/rhinitis | 21 | 20 |
| Chills/fever/sepsis/flu-like symptoms | 13 | 11 |
| CARDIOVASCULAR | ||
| Heart failure/heart failure right | 11 | 13 |
| Myocardial Infarction | 4 | 0 |
| Palpitation | 63 | 71 |
| Shock | 5 | 5 |
| Tachycardia | 43 | 42 |
| Thrombocytopenia | 4 | 0 |
| Vascular disorder peripheral | 96 | 100 |
| Vascular disorder | 95 | 89 |
| GASTROINTESTINAL | ||
| Abdominal enlargement | 4 | 0 |
| Abdominal pain | 14 | 7 |
| Constipation | 4 | 2 |
| Flatulence | 5 | 4 |
| METABOLIC | ||
| Edema/edema peripheral/edema genital | 79 | 87 |
| Hypercalcemia | 48 | 51 |
| Hyperkalemia | 4 | 0 |
| Thirst | 0 | 4 |
| MUSCULOSKELETAL | ||
| Arthritis | 52 | 45 |
| Back pain | 13 | 5 |
| Chest pain | 52 | 45 |
| Cramps leg | 5 | 7 |
| RESPIRATORY | ||
| Cough increase | 82 | 82 |
| Dyspnea | 100 | 100 |
| Epistaxis | 9 | 7 |
| Pharyngitis | 5 | 2 |
| Pleural effusion | 7 | 0 |
| Pneumonia | 5 | 0 |
| Adverse Event* | FLOLAN % n = 56 | Conventional Therapy % n = 55 |
|---|---|---|
| Pneumothorax | 4 | 0 |
| Pulmonary edema | 4 | 2 |
| Respiratory disorder | 7 | 4 |
| Sinusitis | 4 | 4 |
| NEUROLOGICAL | ||
| Anxiety/hyperkinesia/nervousness/tremor | 7 | 5 |
| Depression/depression psychotic | 13 | 4 |
| Hyeresthesia/hypesthesia/paresthesia | 5 | 0 |
| Insomnia | 9 | 0 |
| Somnolence | 4 | 2 |
| SKIN AND APPENDAGES | ||
| Collagen disease | 82 | 84 |
| Pruritus | 4 | 2 |
| Sweat | 41 | 36 |
| UROGENITAL | ||
| Hematuria | 5 | 0 |
| Urinary tract infection | 7 | 0 |
* Table lists adverse events which occurred in at least 2 patients in either group.
Adverse Events Associated with the Drug Delivery System
Chronic infusions of FLOLAN are delivered using a small, portable infusion pump through an indwelling central venous catheter. During controlled idiopathic or heritable PAH trials of up to 12 weeks duration, up to 21% of patients reported a local infection and up to 13% of patients reported pain at the venous catheter insertion site. During a 12 week controlled trial of PAH/SSD, 14% of patients reported a local infection and 9% of patients reported pain at the venous catheter insertion site. During subsequent long-term follow-up in clinical trials of idiopathic or heritable PAH, sepsis/septicemia (mostly related to delivery system for epoprostenol) was reported at least once in 14% of patients and occurred at a rate of 0.32 infections per patient per year in patients treated with FLOLAN. When suspected, sepsis should be diagnosed and treated quickly. It is therefore important that these patients have immediate access to expert medical care. Catheter-related infections caused by organisms not always considered pathogenic (including micrococcus), reddening over the infusion site and occlusion of the long i.v. catheter have been reported. Malfunctions in the delivery system resulting in an inadvertent bolus of, or a reduction in, FLOLAN were associated with symptoms related to excess or insufficient FLOLAN respectively, that may lead to serious consequences including death (see 7 WARNINGS AND PRECAUTIONS, Adverse Events During Chronic Administration, and 5 OVERDOSAGE).
8.5 Post-Market Adverse Reactions
In addition to adverse reactions identified from clinical studies, the following adverse reactions were reported spontaneously to various surveillance systems during post-approval use of FLOLAN.
Cardiovascular Disorders:
- High output cardiac failure
Endocrine Disorders:
- Hyperthyroidism
Blood and Lymphatic Disorders:
- Very rare cases of splenomegaly and hypersplenism have been observed in the Portopulmonary Hypertension subpopulation of Pulmonary Arterial Hypertension patients treated with FLOLAN.
Gastrointestinal Disorders:
- Very rare cases of ascites associated with long-term epoprostenol use have been observed in Pulmonary Arterial Hypertension patients treated with FLOLAN.
9 DRUG INTERACTIONS
9.2 Drug Interactions Overview
Additional reductions in blood pressure may occur when FLOLAN is administered with diuretics, antihypertensive agents, or other vasodilators. When NSAIDS or other drugs affecting platelet aggregation are used concomitantly, there is the potential for FLOLAN to increase the risk of bleeding. In clinical trials, FLOLAN was used with digoxin, diuretics, anticoagulants, oral vasodilators and supplemental oxygen.
9.4 Drug-Drug Interactions
The vasodilator effects of FLOLAN may augment or be augmented by concomitant use of other vasodilators.
In a pharmacokinetic substudy in patients with congestive heart failure receiving furosemide or digoxin in whom FLOLAN therapy was initiated, apparent oral clearance values for furosemide (n=23) and digoxin (n=30) were decreased by 13% and 15%, respectively, on the second day of therapy and returned to baseline values by day 87. The change in furosemide clearance value is not likely to be clinically significant. However, patients on digoxin may show elevations of digoxin concentrations after initiation of therapy with FLOLAN, which may be clinically significant in patients prone to digoxin toxicity.
9.5 Drug-Food Interactions
Interactions with food have not been established.
9.6 Drug-Herb Interactions
Interactions with herbal products have not been established.
9.7 Drug-Laboratory Test Interactions
Interactions with laboratory tests have not been established.
10 CLINICAL PHARMACOLOGY
10.1 Mechanism of Action
FLOLAN, also known as prostacyclin, PGl2 or PGX, a metabolite of arachidonic acid, is a naturally occurring prostaglandin. Epoprostenol has two major pharmacological actions: (1) direct vasodilation of pulmonary and systemic arterial vascular beds, and (2) inhibition of platelet aggregation.
10.2 Pharmacodynamics
In animals, the vasodilatory effects of epoprostenol reduce right and left ventricular afterload and increase cardiac output and stroke volume. The effect of epoprostenol on heart rate in animals varies with dose. At low doses, there is vagally mediated bradycardia, but at higher doses, epoprostenol causes reflex tachycardia in response to direct vasodilation and hypotension. No major effects on cardiac conduction have been observed. Additional pharmacologic effects of epoprostenol in animals include bronchodilation, inhibition of gastric acid secretion, and decreased gastric emptying.
Cardiovascular Pharmacology: Epoprostenol sodium produces vascular relaxation in vitro, and systemic, pulmonary, and coronary vasodilation in vivo without significant electrocardiographic effects.
In anaesthetized rats, epoprostenol sodium (0.125-64 μg/kg I.V.) caused dose-dependent decreases in systolic and diastolic blood pressures (up to 100 mm Hg) along with tachycardia (up to 66 beats/min) which was reflex in origin. Dose-dependent reductions in mean arterial blood pressure (up to 40 mm Hg) accompanied by tachycardia (up to 80 beats/min) were observed in conscious rats receiving 0.1-1 μg/kg/min I.V.
In anaesthetized dogs, epoprostenol sodium (0.01-0.3 μg/kg/min I.V.) produced dose-dependent decreases in total peripheral resistance (27-61%), mean arterial blood pressure (15-61%), and pulmonary vascular resistance (32-44%), and increases in cardiac output which were a function of dose-dependent increases in stroke volume (+40% at 0.3 μg/kg/min).
In conscious dogs, intra-arterial administration of epoprostenol sodium (0.1-1 μg/kg/min) effected dose-dependent decreases in left ventricular work (-39% at 1 μg/kg/min) and mean arterial blood pressure (-28% at 1 μg/kg/min). Pulmonary artery and renal artery blood flows were increased by 45% and 43% respectively at the highest dose, while most other organs showed dose-dependent decreases in blood flow.
The hypoxia-induced increases in pulmonary arterial blood pressure and pulmonary vascular resistance in anaesthetized cats were respectively reduced (by 70%) and abolished by epoprostenol sodium (0.3 μg/kg/min I.V.).
The effects of epoprostenol sodium are mediated through a specific membrane receptor, with signal transduction through the adenylate cyclase/cAMP secondary messenger system.
Endocrine Effects: The effects of epoprostenol sodium on the circulating levels of anterior pituitary hormones was studied in rats. Although 1 mg/kg epoprostenol sodium given subcutaneously for seven consecutive days was a no-effect dose, 60 mg/kg/day produced decreased plasma leuteinizing hormone but had no effect on follicle stimulating hormone. There were no significant differences in pituitary weights and no drug-related lesions were found by light-microscopy. In a primate luteolysis screening bioassay, 11.5 mg/kg epoprostenol sodium given by intramuscular injection did not produce signs of luteolysis (decreased levels of progesterone).
Subcutaneous injection of 30 mg/kg epoprostenol sodium in two male patas monkeys produced a prominent and persistent increase in plasma cortisol but did not affect either thyroid hormone T3 or T4.
Gastrointestinal Effects: Epoprostenol sodium produces dose-dependent in vivo and in vitro inhibition of gastric acid secretion induced by histamine and pentagastrin in rats and rat isolated tissue. Dose-dependent inhibition of ethanol-induced gastric lesions in rats has been observed. Gastric emptying may be decreased.
Neuropharmacological Effects: Epoprostenol sodium administered as a single intravenous bolus to conscious mice (1-10 mg/kg) and rats (0.1 μg/kg-100 mg/kg) exerts relatively minor behavioural effects until high doses are achieved. Decreases in body temperature and peripheral flushing are commonly observed secondary to the vasodilation caused by this agent.
Platelet Aggregation: Epoprostenol sodium is the most potent inhibitor of platelet aggregation known, with profound inhibition of aggregation observed in virtually all species, both in vivo and ex vivo. Increased bleeding times were observed in rats and dogs.
Renal Effects: Under basal conditions, epoprostenol sodium causes equivocal changes in urine output and ion excretion. Renal function following ischemia is preserved by treatment with epoprostenol sodium. In rabbits, epoprostenol caused a dose dependent reduction in glomerular filtration rate.
Respiratory Effects: Epoprostenol sodium has bronchodilator effects in guinea pigs and dogs exposed to the bronchoconstriction induced by histamine, acetylcholine and PGF2α.
10.3 Pharmacokinetics
Animal studies using tritium-labelled epoprostenol have indicated a high clearance (93 mL/min/kg), small volume of distribution (357 mL/kg), and a short half-life (2.7 minutes). During infusions in animals, steady-state plasma concentrations of tritium-labelled epoprostenol were reached within 15 minutes and were proportional to infusion rates.
No available chemical assay is sufficiently sensitive and specific to assess the in vivo human pharmacokinetics of epoprostenol. The in vitro half-life of epoprostenol in human blood at 37°C and pH 7.4 is approximately 6 minutes; the in vivo half-life of epoprostenol in humans is therefore expected to be no greater than 6 minutes. The in vitro pharmacologic half-life of epoprostenol in human plasma, based on inhibition of platelet aggregation, is 10.6 minutes in males (n = 954) and 10.8 minutes in females (n = 1024).
Tritium-labelled epoprostenol has been administered to humans in order to identify the metabolic products of epoprostenol. Epoprostenol is metabolized to 6-keto-PGF1α (formed by spontaneous degradation) and 6,15-diketo-13,14-dihydro-PGF1α (enzymatically formed), both of which have pharmacological activity at orders of magnitude less than epoprostenol in animal test systems. The recovery of radioactivity in urine and feces over a one-week period was 82% and 4% of the administered dose, respectively. Fourteen additional minor metabolites have been isolated from urine, indicating that epoprostenol is extensively metabolized in humans.
Absorption: Epoprostenol is rapidly hydrolyzed at neutral pH in blood and is also subject to enzymatic degradation. In one study in rabbits, after a 107 mg/kg bolus I.V. dose of 3H-epoprostenol sodium, clearance was 93 mL/min/kg, volume of distribution was 357 mL/kg, and the terminal half-life was 2.7 min.
In a separate study in rabbits, after an 85 mg/kg dose of 3H-epoprostenol sodium, clearance was 256 mL/min/kg, volume of distribution was 1015 mL/kg, and the terminal half-life was 2.9 min. When rabbits were given intravenous infusions of tritiated epoprostenol sodium (ranging from 4.2 to 604 ng/kg/min), plasma steady-state concentrations were achieved within 15 minutes of initiation of the infusions, and steady-state concentrations increased linearly with increasing infusion rate. A study performed in cats (100 ng/kg/min of 3H-epoprostenol sodium) using the same analytical methodology, indicated that steady state was achieved by 60 minutes after initiation of the infusion.
Distribution: Tissue distribution studies have been performed in rats given either intravenous or subcutaneous doses of tritiated epoprostenol sodium. Tritium concentrations declined rapidly after either route of administration. The highest levels of radioactivity were observed in the kidney, liver, and small intestine and the lowest levels were observed in brain and adipose tissue. After an I.V. dose, approximately one-third of the radioactivity was detected in the liver 15 minutes after dosing.
Metabolism: Epoprostenol undergoes rapid chemical hydrolysis under physiological conditions to yield 6-keto-PGF1α. In addition, the metabolism of epoprostenol involves dehydrogenation of the C-15 hydroxyl group, reduction of the 13,14-trans double bond, β-oxidation, ω or ω-1 oxidation. Metabolites consistent with all these metabolic reactions were observed in in vitro and in vivo studies in rats, dogs and monkeys. In addition, glucuronide-conjugated metabolites have been isolated from rat bile after epoprostenol sodium administration. Cytochrome P-450-dependent epoxidation of epoprostenol has been described in vitro. All of the metabolites reported in animal studies are essentially inactive, with the exception of 6-keto-PGE1, that has been detected in dogs but not in any other species. Liver and kidney may be the most important organs with respect to metabolism.
Elimination: Epoprostenol-derived material is rapidly excreted into urine and feces after dosing with epoprostenol sodium. Dogs excrete nearly 90% of the administered dose in the urine, while in rats there was a more balanced distribution into urine and feces. Monkeys excreted 45.2% of the dose into urine, but fecal recovery was not determined.
11 STORAGE, STABILITY AND DISPOSAL
Vials
Store the vials of FLOLAN at 15° to 25°C. Protect from light.
Store the vials of pH 12 STERILE DILUENT for FLOLAN at 15° to 25°C. DO NOT FREEZE.
Reconstituted Solutions
FLOLAN is only stable when reconstituted with pH 12 STERILE DILUENT for FLOLAN (see 4.4 Administration).
Do not freeze reconstituted solutions of FLOLAN. A Cold Pouch is NOT required during administration. Protect from light when stored or in use.
Freshly prepared reconstituted solutions or reconstituted solutions that have been stored at 2° to 8°C (36° to 46°F) for no longer than 8 days can be administered up to:
- 48 hours at up to 25°C (77°F)
- 36 hours at up to 30°C (86°F)
- 24 hours at up to 35°C (95°F)
- 12 hours at up to 40°C (104°F)
Discard any unused solution after this time.
FLOLAN solution prepared with pH 12 STERILE DILUENT for FLOLAN must not be used with any preparation or administration materials containing PET or PETG. Preparation and administration materials containing PET or PETG may become damaged when used with FLOLAN solution prepared with pH 12 STERILE DILUENT for FLOLAN.
12 SPECIAL HANDLING INSTRUCTIONS
There are special handling instructions indicated in previous sections (see 4.3 Reconstitution and 11 STORAGE, STABILITY AND DISPOSAL).
PART II: SCIENTIFIC INFORMATION
13 PHARMACEUTICAL INFORMATION
Drug Substance
Common name: Epoprostenol sodium
Chemical name [USAN]: Prosta-5,13-dien-1-oic acid, 6,9-epoxy-11,15-dihydroxy-, sodium salt, (5Z, 9α, 11α, 13E, 15S)
Chemical name [Chem. Abstr.]: (5Z, 9α, 11α, 13E, 15S)-6,9-Epoxy-11,15-dihydroxyprosta-5,13-dien-1-oic acid monosodium salt)
Molecular formula and molecular mass: C20H31NaO5, 374.45
Structural formula [USAN]:
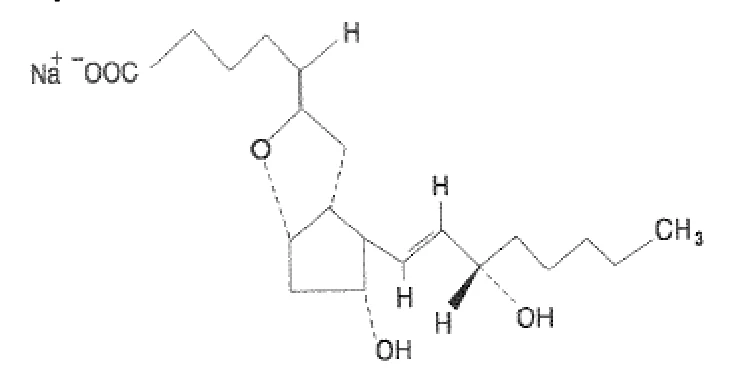
Physicochemical properties: Epoprostenol sodium is a white to off-white solid which melts over a wide range of temperatures with decomposition. It is readily soluble in water and ethanol, and sparingly soluble in acetonitrile.
14 CLINICAL TRIALS
14.1 Clinical Trials by Indication
Hemodynamic effects of FLOLAN in Pulmonary Arterial Hypertension (PAH):
Acute Hemodynamic effects
Acute intravenous infusions of FLOLAN for up to 15 minutes in patients with idiopathic or heritable PAH or PAH/SSD, produced dose-related increases in cardiac index (Cl) and stroke volume (SV), and dose-related decreases in pulmonary vascular resistance (PVR), total pulmonary resistance (TPR), and mean systemic arterial pressure (SAPm). The effects of FLOLAN on mean pulmonary arterial pressure (PAPm) were variable and minor.
Chronic Hemodynamic effects
Chronic hemodynamic effects in patients with idiopathic or heritable PAH were generally similar to acute effects. Cl, SV, and arterial oxygen saturation were increased, and PAPm, right atrial pressure (RAP), TPR, and systemic vascular resistance (SVR) were decreased in patients who received FLOLAN chronically, compared to those who did not.
Table 13 illustrates the treatment-related hemodynamic changes in these patients after 8 or 12 weeks of treatment.
Table 13 - Hemodynamics During Chronic Administration of FLOLAN in Patients with Idiopathic or Heritable PAH
Hemodynamic Parameter | Baseline | Mean change from baseline at end of treatment period* | ||||||||||
|---|---|---|---|---|---|---|---|---|---|---|---|---|
FLOLAN (n = 52) | Conventional Therapy (n = 54) | FLOLAN (n = 48) | Conventional Therapy (n = 41) | |||||||||
CI (L/min/m2) | 2.0 | 2.0 | 0.3** | -0.1 | ||||||||
PAPm (mm Hg) | 60 | 60 | -5** | 1 | ||||||||
PVR (Wood U) | 16 | 17 | -4** | 1 | ||||||||
SAPm (mm Hg) | 89 | 91 | -4 | -3 | ||||||||
SV (mL/beat) | 44 | 43 | 6** | -1 | ||||||||
TPR (Wood U) | 20 | 21 | -5** | 1 | ||||||||
*At 8 weeks: FLOLAN n = 10; Conventional Therapy n = 11 (n is the number of patients with hemodynamic data).
At 12 weeks: FLOLAN n = 38; Conventional Therapy n = 30 (n is the number of patients with hemodynamic data)
**Denotes statistically significant difference between FLOLAN and Conventional Therapy groups
CI = cardiac index; PAPm = mean pulmonary arterial pressure; PVR = pulmonary vascular resistance;
SAPm = mean systemic arterial pressure; SV = stroke volume ; TPR = total pulmonary resistance
Survival
Survival was improved in New York Heart Association (NYHA) functional Class III and Class IV patients with idiopathic or heritable PAH treated with FLOLAN for 12 weeks in a multicenter, open, randomized, parallel, controlled study. At the end of the treatment period, 8 of 40 patients receiving standard therapy alone had died, whereas none of the 41 patients receiving FLOLAN had died (p=0.003).
Chronic Infusion in PAH/SDD:
Hemodynamic effects
Chronic continuous infusions of FLOLAN in patients with PAH/SSD were studied in a prospective, open, randomized trial of 12 weeks duration comparing FLOLAN plus conventional therapy to conventional therapy alone. Except for the five NYHA functional Class II patients, all patients were either functional Class III or Class IV. The patients principally had pulmonary vascular manifestations of the collagen-vascular disease, with minimal evidence of interstitial lung disease and with total lung capacities greater than 60% of the predicted normal. Dosage of FLOLAN was determined as described in 4 DOSAGE AND ADMINISTRATION and averaged 11.2 ng/kg per minute at study end. Conventional therapy varied among patients and included oxygen and diuretics in two-thirds of the patients, oral vasodilators in 40% of the patients, and digoxin in a third of the patients. A statistically significant increase in CI, and statistically significant decreases in PAPm, RAP, PVR, and SAPm were observed in patients who received FLOLAN chronically compared to those who did not. Table 14 illustrates the treatment-related hemodynamic changes in these patients after 12 weeks of treatment.
Table 14 - Hemodynamics During Chronic Administration of FLOLAN in Patients with PAH/SSD
Hemodynamic Parameter | Baseline | Mean change from baseline at 12 weeks | ||||||||
|---|---|---|---|---|---|---|---|---|---|---|
FLOLAN (n = 56) | Conventional Therapy (n = 55) | FLOLAN (n = 50) | Conventional Therapy (n = 48) | |||||||
PAPm (mm Hg) | 51 | 49 | -5* | 1 | ||||||
RAP (mm Hg) | 13 | 11 | -1* | 1 | ||||||
PVR (Wood U) | 14 | 11 | -5* | 1 | ||||||
SAPm (mm Hg) | 93 | 89 | -8* | -1 | ||||||
* Denotes statistically significant difference between FLOLAN and Conventional Therapy groups (n is the number of patients with hemodynamic data).
CI = cardiac index; PAPm = mean pulmonary arterial pressure; RAP = right atrial pressure; PVR = pulmonary vascular resistance; SAPm = mean systemic arterial pressure
Clinical effects
Statistically significant improvement was observed in exercise capacity, as measured by the 6-minute walk, in patients receiving continuous intravenous FLOLAN plus conventional therapy for 12 weeks compared to those receiving conventional therapy alone. Improvements were apparent as early as the first week of therapy. Increases in exercise capacity were accompanied by statistically significant improvements in dyspnea and fatigue, as measured by the Borg Dyspnea Index and Dyspnea Fatigue Index. By week 12, NYHA Functional Class improved in 21 of 51 (41%) patients treated with FLOLAN compared to none of the 48 patients treated with conventional therapy alone.
No statistical difference in survival over 12 weeks was observed in PAH/SSD patients treated with FLOLAN. At the end of the treatment period, 4 of 56 (7%) patients receiving FLOLAN died, whereas 5 of 55 (9%) patients receiving conventional therapy died.
15 MICROBIOLOGY
No microbiological information is required for this drug product.
16 NON-CLINICAL TOXICOLOGY
General Toxicology:
Acute Toxicity Studies
Rodents: The acute toxicity of epoprostenol sodium was determined in rodents as shown in Table 15.
Table 15 - Acute Toxicity of Epoprostenol Sodium in Rodents
| Strain/Species | No. per Group | Dose (mg/kg) | Route | LD50 (mg/kg) |
|---|---|---|---|---|
| Evans-1 mouse | 10M, 10F | 0, 0.1, 0.3, 1, 10 | I.V. | > 10 |
| Evans-1 mouse | 10M, 0F | 0, 0.003, 0.03, 0.1, 0.3, 1 | I.V. | - |
| Wistar rat | 5M, 5F | 0, 0.0001, 0.01, 1, 100 | I.V. | 66.3 |
| 25, 35, 50, 70, 80, 100 |
The LD50 in mice could not be estimated since the maximum dose level of 10 mg/kg epoprostenol was lethal in only 1 of 10 male and in none of 10 female mice.
Epoprostenol 0.0001 mg/kg was without effect. The effects of epoprostenol sodium were observed in mice given doses as low as 0.003 mg/kg. Flaccid paralysis, hypoactivity, ataxia, lost or weak righting reflex, slow and/or deep laboured breathing, ptosis and piloerection were observed following doses of epoprostenol greater than 0.01 mg/kg I.V. Signs of toxicity observed 2 to 5 minutes postdose with 0.03 to 10 mg/kg included decreased activity, bradypnea, hypothermia, ataxia, and skin flushing. These signs disappeared in 2 hours postdose. Dose-related hypothermia, which occurred slightly later than the other signs, was most prominent 10 minutes following dosing, but undetectable at 2 hours postdose. With the exception of pulmonary hemorrhage in one male mouse receiving 10 mg/kg, there were no gross lesions in any other animal. Rats given intravenous doses of 100 mg/kg developed respiratory distress, collapsed and died 1 to 10 minutes postdose.
Table 16 - Subacute and Subchronic Toxicity Studies
Strain/ Species | No. per Group | Doses | Route | Duration (days) | Drug-related Findings |
|---|---|---|---|---|---|
| SD Rat | 5M, 5F | 0, 56, 180, 560 ng/kg/min | continuous I.V. | 14 | Weight loss, reddened skin, and decreased platelet counts. |
| Beagle Dog | 2M, 2F | 0, 12.5, 40, 125 ng/kg/min | continuous I.V. | 30 | Emesis, soft feces, decreased platelet counts, Significantly decreased white blood cells. |
| Beagle Dog | 2M, 2F | 125 ng/kg/min | continuous I.V. | 30 | Platelet decreases and hematologic changes reversed. |
Monkey (Erythrocebus patas) | 2M, 2F | 0, 0.01, 0.1, 1 μg/kg/min | I.V. (1 hr/day 3 X/wk) | 14 | Emesis, diarrhea, decreased blood pressure, tachycardia, focal necrosis in heart (1 monkey), bleeding time and blood glucose significantly increased. |
| Wistar Rat | 0M, 2F | 0, 1, 10, 30, 60 mg/kg | S.C. | 7 | Hypotension, EKG changes (myocardial ischemia), necrosis in heart. |
| Wistar Rat | 15M, 15F | 0, 1, 10, 100 μg/kg | S.C. | 14 | Red skin, hypotension, EKG changes (myocardial ischemia). |
Monkey (Erythrocebus patas) | 1M, 0F | Dose escalation 0, 1, 10, 30, 60, 60 mg/kg | S.C. | 5 | Red skin, hypotension (all doses); necrosis in heart. |
Carcinogenicity: Carcinogenesis bioassays have not been performed with epoprostenol sodium.
Genotoxicity: Preliminary studies showed that epoprostenol sodium was non-mutagenic in the Ames Salmonella assay, non-clastogenic in the rat micronucleus assay, and did not damage DNA in the alkaline elution assay (see Table 17 below).
Table 17 - Mutagenicity Assays with Epoprostenol Sodium
1 Not applicable
Reproductive and Developmental Toxicology: In a Segment I reproduction study in rats, males were treated with 0, 10, 30, or 100 μg/kg/day subcutaneous epoprostenol sodium for 60 days prior to mating and during a 14-day mating period. Females were treated 14 days before mating and during mating, gestation and lactation. There were no signs of treatment-related effects on fertility of either the parental generation or the first filial generation rats. Estrus cycles of the F0 dams were normal. Pregnancies, developmental milestones and behavioural tests were all judged to be normal.
There was no teratogenic effect in fetuses from rats and rabbits given epoprostenol sodium by subcutaneous injection during critical periods of organogenesis at dose levels of 1, 10 and 100 μg/kg/day. Gestation, parturition, and the rearing of young were all normal in rats given subcutaneous doses of 0, 10, 30 and 100 μg/kg/day.
Table 18 - Reproduction Studies with Epoprostenol Sodium
| Study | Strain/ Species | No. per Group | Route | Dose and Frequency | Drug-related Findings |
|---|---|---|---|---|---|
Segment I Fertility | SD Rat | 12M, 24F | S.C. | 0, 10, 30, 100 μg/kg/day (60 days) | Depression (all doses), ataxia (30 and 100 μg/kg); no effect on fertility. |
Segment II Teratology | Wistar Rat | 20F | S.C. | 0, 1, 10, 100 μg/kg/day Gestational days 6-16 | No teratogenic effects. |
Segment III Peri-postnatal | SD Rat | 24F | S.C. | 0, 10, 30, 100 μg/kg/day Gestational day 15 through Postpartum day 21 | Depression (all doses), ataxia (30 and 100 μg/kg); slightly delayed parturition; pup survival significantly decreased. |
Segment II Teratology | DB Rabbit | 15F | S.C. | 0, 1, 10, 100 μg/kg/day Gestational days 6-18 | No obvious teratogenic effects; technical difficulties with the study. |
Segment II Teratology | DB Rabbit | 44F | S.C. | 0, 100 μg/kg/day Gestational days 6-18 | Red skin, hypotension. No teratogenic effects. |
| Study | Species | No. per Group | Dose/Concentration | Duration |
|---|---|---|---|---|
| Ames assay | Salmonella typhimurium | NA1 | Up to 2000 μg/plate | NA |
| Micronucleus assay | Rat | 10M, 0F | 0, 10, 20, 40 mg/kg i.p. | 1 day |
| Alkaline Elution assay | in vitro | NA | Up to 3 mM concentration | NA |
Special Toxicology
Dermal Irritation: Epoprostenol sodium at a dose of 0.1 mL (1 mg/mL concentration) applied three times in one day to abraded skin of CFLP mice produced no histopathologic alterations.
Toxicity of Hydrolysis Product: The subacute toxicity of 6-keto-PGF1α an epoprostenol hydrolysis product, was investigated in patas monkeys. A dose of 1 μg/kg/min given as a 60-minute intravenous infusion 3 times per week for 2 weeks was devoid of toxic and pharmacodynamic activity.