


Product Monograph - Teva-Ticagrelor
RECENT MAJOR LABEL CHANGES
| 7 WARNINGS AND PRECAUTIONS, Cardiovascular | 01/2023 |
|---|---|
| 7 WARNINGS AND PRECAUTIONS, Central Sleep Apnea | 01/2023 |
| 1 INDICATIONS | 11/2024 |
| 1 INDICATION, 1.2 Geriatrics | 11/2024 |
| 4 DOSAGE AND ADMINISTRATION, 4.1 Dosing Considerations | 11/2024 |
| 4 DOSAGE AND ADMINISTRATION, 4.2 Recommended Dose and Dosage Adjustment | 11/2024 |
| 7 WARNINGS AND PRECAUTIONS, General | 11/2024 |
| 7 WARNINGS AND PRECAUTIONS, Cardiovascular | 11/2024 |
| 7 WARNINGS AND PRECAUTIONS, Neurologic | 11/2024 |
| 7 WARNINGS AND PRECAUTIONS, Respiratory | 11/2024 |
| 7 WARNINGS AND PRECAUTIONS, 7.1.3 Pediatrics | 11/2024 |
| 7 WARNINGS AND PRECAUTIONS, 7.1.4 Geriatrics | 11/2024 |
Table of Contents
RECENT MAJOR LABEL CHANGES ............................................................................................. 2
PART I: HEALTH PROFESSIONAL INFORMATION ....................................................................... 4
1 INDICATIONS ................................................................................................................. 4
1.1 Pediatrics .................................................................................................................... 4
1.2 Geriatrics ..................................................................................................................... 4
2 CONTRAINDICATIONS ................................................................................................... 4
4 DOSAGE AND ADMINISTRATION ................................................................................... 5
4.1 Dosing Considerations................................................................................................. 5
4.2 Recommended Dose and Dosage Adjustment ............................................................ 5
4.4 Administration ............................................................................................................ 7
4.5 Missed Dose ................................................................................................................ 8
5 OVERDOSAGE ............................................................................................................... 8
6 DOSAGE FORMS, STRENGTHS, COMPOSITION AND PACKAGING ................................... 9
7 WARNINGS AND PRECAUTIONS .................................................................................... 9
7.1 Special Populations ................................................................................................... 14
7.1.1 Pregnant Women .................................................................................................. 14
7.1.2 Breast-feeding ....................................................................................................... 14
7.1.3 Pediatrics ............................................................................................................... 14
7.1.4 Geriatrics .................................................................................................................... 15
8 ADVERSE REACTIONS .................................................................................................. 15
8.1 Adverse Reaction Overview ...................................................................................... 15
8.2 Clinical Trial Adverse Reactions ................................................................................. 17
8.3 Less Common Clinical Trial Adverse Reactions .......................................................... 26
8.4 Abnormal Laboratory Findings: Hematologic, Clinical Chemistry and Other Quantitative Data ................................................................................................................ 27
8.5 Post-Market Adverse Reactions ................................................................................ 28
9 DRUG INTERACTIONS .................................................................................................. 28
9.1 Serious Drug Interactions .......................................................................................... 28
9.2 Drug Interactions Overview ...................................................................................... 29
9.3 Drug-Behavioural Interactions .................................................................................. 29
9.4 Drug-Drug Interactions ............................................................................................. 29
9.5 Drug-Food Interactions ............................................................................................. 32
9.6 Drug-Herb Interactions ............................................................................................. 33
9.7 Drug-Laboratory Test Interactions ............................................................................ 33
10 CLINICAL PHARMACOLOGY ......................................................................................... 33
10.1 Mechanism of Action ............................................................................................. 33
10.2 Pharmacodynamics ............................................................................................... 34
10.3 Pharmacokinetics .................................................................................................. 36
11 STORAGE, STABILITY AND DISPOSAL ........................................................................... 40
12 SPECIAL HANDLING INSTRUCTIONS ............................................................................. 40
PART II: SCIENTIFIC INFORMATION ....................................................................................... 41
13 PHARMACEUTICAL INFORMATION .............................................................................. 41
14 CLINICAL TRIALS .......................................................................................................... 42
14.1 Clinical Trials by Indication .................................................................................... 42
Acute Coronary Syndrome .................................................................................................. 42
Patients with History of Myocardial Infarction (≥One Year) ................................................ 46
Patients with Coronary Artery Disease and Type 2 Diabetes Mellitus with a History of Percutaneous Coronary Intervention .................................................................................. 50
14.2 Comparative Bioavailability Studies ...................................................................... 55
15 MICROBIOLOGY .......................................................................................................... 55
16 NON-CLINICAL TOXICOLOGY ....................................................................................... 55
17 SUPPORTING PRODUCT MONOGRAPHS ...................................................................... 57
PATIENT MEDICATION INFORMATION ............................................................................... 58
PART I: HEALTH PROFESSIONAL INFORMATION
1 INDICATIONS
Acute Coronary Syndrome
Teva-Ticagrelor (Ticagrelor Tablets), co-administered with low-dose acetylsalicylic acid (ASA: 75-150 mg), is indicated for the secondary prevention of atherothrombotic events in patients with acute coronary syndromes (ACS) (see 14 CLINICAL TRIALS).
History of Myocardial Infarction (at least one year ago)
Teva-Ticagrelor (ticagrelor), co-administered with low-dose acetylsalicylic acid (ASA: 75-150 mg), is indicated for the secondary prevention of atherothrombotic events in patients with a history of myocardial infarction (MI occurred at least one year ago) and a high risk of developing an atherothrombotic event (see 14 CLINICAL TRIALS).
Coronary Artery Disease, Type 2 Diabetes Mellitus and History of Percutaneous Coronary Intervention
Teva-Ticagrelor (ticagrelor), co-administered with low-dose acetylsalicylic acid (ASA: 75-150 mg), is indicated to reduce the risk of a first myocardial infarction or stroke in patients with Coronary Artery Disease (CAD), Type 2 Diabetes Mellitus (DM), and a history of percutaneous coronary intervention (PCI), who are also at high risk of developing an atherothrombotic event (see 4 DOSAGE AND ADMINISTRATION, 7 WARNINGS AND PRECAUTIONS and 14 CLINICAL TRIALS).
1.1 Pediatrics
Pediatrics (< 18 years of age): The safety and efficacy of ticagrelor in pediatric patients below the age of 18 have not been established. Therefore, Health Canada has not authorized an indication for pediatric use. See 7.1.3 Pediatrics.
1.2 Geriatrics
Geriatrics (≥ 65 years): No overall differences in safety or efficacy were observed between geriatric patients and younger adult patients with acute coronary syndrome (PLATO), a history of MI (≥one year) (PEGASUS), or with CAD, type 2 DM and a history of PCI (THEMIS) (see 8 ADVERSE REACTIONS and 14 CLINICAL TRIALS).
2 CONTRAINDICATIONS
Teva-Ticagrelor (ticagrelor) is contraindicated in:
- Patients who are hypersensitive to this medication or to any ingredient in the formulation. For a complete listing of ingredients, see 6 DOSAGE FORMS, STRENGTHS, COMPOSITION AND PACKAGING.
- Patients who have active pathological bleeding such as peptic ulcer or intracranial hemorrhage (see 7 WARNINGS AND PRECAUTIONS and 8 ADVERSE REACTIONS).
- Patients with a history of intracranial hemorrhage (see 7 WARNINGS AND PRECAUTIONS and 8 ADVERSE REACTIONS).
- Patients with moderate to severe hepatic impairment (see 4 DOSAGE AND ADMINISTRATION and 10 CLINICAL PHARMACOLOGY).
- Patients who are also taking strong CYP3A4 inhibitors (e.g. ketoconazole, clarithromycin, nefazodone, ritonavir, and atazanavir) (see 7 WARNINGS AND PRECAUTIONS and 9 DRUG INTERACTIONS).
4 DOSAGE AND ADMINISTRATION
4.1 Dosing Considerations
Patients taking Teva-Ticagrelor should also take a daily low maintenance dose of ASA 75-150 mg, unless specifically contraindicated.
In patients with ACS who have undergone a PCI procedure and have an increased risk of bleeding discontinuation of ASA may be considered after 3 months (see 7 WARNINGS AND PRECAUTIONS).
The PLATO trial data suggest the efficacy of ticagrelor 90 mg bid relative to clopidogrel 75 mg od is associated with ASA dose during maintenance therapy. Patients receiving a low maintenance dose of ASA benefit more than those receiving a high maintenance dose of ASA. Because the data from patients receiving high maintenance dose ASA (> 300 mg daily) do not provide conclusive evidence of the efficacy of ticagrelor 90 mg bid compared to clopidogrel 75 mg od, high maintenance dose ASA (> 150 mg daily) is not recommended for maintenance dual antiplatelet therapy with Teva-Ticagrelor 90 mg. There is no conclusive evidence regarding the underlying biological mechanism (see 14 CLINICAL TRIALS).
4.2 Recommended Dose and Dosage Adjustment
Acute Coronary Syndrome
Teva-Ticagrelor 90 mg therapy should be initiated with a single 180 mg oral loading dose (two 90 mg tablets) and then continued at 90 mg twice daily.
Switching from clopidogrel to Teva-Ticagrelor 90 mg:
Patients can be switched from clopidogrel to Teva-Ticagrelor without interruption of antiplatelet effect. This results in an absolute inhibition of platelet aggregation (IPA) increase of 26.4%. Conversely, switching from ticagrelor 90 mg twice daily to clopidogrel 75 mg results in an absolute IPA decrease of 24.5%. Clinicians who desire to switch patients, with a prior ACS event, from clopidogrel to Teva-Ticagrelor should administer the first dose of Teva-Ticagrelor 24 hours following the last dose of clopidogrel (see 10.2 Pharmacodynamics).
History of Myocardial Infarction (≥One Year)
Teva-Ticagrelor 60 mg twice daily is the recommended dose when an extended treatment is required for patients with a history of spontaneous MI of at least one year and at high risk of developing an atherothrombotic event. No loading dose of Teva-Ticagrelor is required. The Teva-Ticagrelor 90 mg dose should not be used for this indication (see 14 CLINICAL TRIALS).
Teva-Ticagrelor 60 mg may be started without interruption after the initial one-year treatment with Teva-Ticagrelor 90 mg or other adenosine diphosphate (ADP) receptor antagonist therapy in ACS patients at high risk of an atherothrombotic event.
Treatment can also be initiated up to two years from the spontaneous myocardial infarction, or within one year after stopping previous ADP receptor antagonist treatment (see 14 CLINICAL TRIALS).
Treatment with Teva-Ticagrelor should be continued in patients with a history of MI for as long as the patient remains at high risk of an atherothrombotic event for a duration up to three years. Efficacy and safety data are insufficient to establish whether the benefits of Teva-Ticagrelor still outweigh the risks after three years of extended treatment.
Switching from another P2Y12 receptor antagonist to Teva-Ticagrelor 60 mg in patients with a history of MI:
Physicians who desire to switch patients with a history of MI to Teva-Ticagrelor should administer the first dose of Teva-Ticagrelor 24 hours following the last dose of the other P2Y12 receptor antagonist.
Patients with Coronary Artery Disease (CAD) and Type 2 Diabetes Mellitus (DM) with a history of percutaneous coronary intervention (PCI)
Teva-Ticagrelor 60 mg twice daily is the recommended dose for patients with CAD and type 2 DM with a history of PCI with no prior MI. No loading dose of Teva-Ticagrelor is required.
Patients may start treatment with Teva-Ticagrelor 60 mg twice daily, regardless of their previous antiplatelet regimen.
Treatment with Teva-Ticagrelor should be continued in patients with CAD and type 2 DM for as long as the patient remains at high risk of an atherothrombotic event and low risk of bleeding, for a duration up to three years. Efficacy and safety data are insufficient to establish whether the benefits of Teva-Ticagrelor still outweigh the risks after three years of treatment (see 7 WARNINGS AND PRECAUTIONS and 14 CLINICAL TRIALS).
Switching from another P2Y12 receptor antagonist to Teva-Ticagrelor 60 mg in patients with CAD and Type 2 DM and a history of PCI: Physicians who desire to switch patients with CAD and Type 2 DM and a history of PCI to Teva-Ticagrelor should administer the first dose of Teva-Ticagrelor 24 hours following the last dose of the other P2Y12 receptor antagonist.
Premature Discontinuation
Premature discontinuation with any antiplatelet therapy, including Teva-Ticagrelor, could result in an increased risk of cardiovascular (CV) death or MI due to the patient’s underlying disease (see 7 WARNINGS AND PRECAUTIONS).
Dosing Considerations in Special Populations
Geriatrics (≥ 65 years of age): No dosage adjustment is required in elderly (≥ 65 years) patients (see Special Populations and Conditions).
Patients with Renal Insufficiency: No dosage adjustment is required in patients with renal impairment. Ticagrelor is not dialyzable. Appropriate caution should be used in patients requiring renal replacement therapy (see Special Populations and Conditions).
Patients with Hepatic Insufficiency: No dosage adjustment is required in patients with mild hepatic impairment. No studies have specifically been conducted for ticagrelor in patients with moderate or severe hepatic impairment. There is only limited information on the treatment of patients with moderate hepatic impairment. Therefore, use in patients with moderate or severe hepatic impairment is contraindicated (see 2 CONTRAINDICATIONS and Special Populations and Conditions).
4.4 Administration
Timing of administration of a dose with respect to food
Teva-Ticagrelor may be taken orally with or without food, may be given without regard to meals. In a study of healthy subjects, ingestion of a high-fat meal had no effect on ticagrelor Cmax or the AUC of the active metabolite, but resulted in a 21% increase in ticagrelor AUC and 22% decrease in the active metabolite Cmax. These changes are considered of minimal clinical significance. Ticagrelor was administered without regard to food in PLATO (90 mg), PEGASUS (60 mg) and THEMIS (60 mg).
Alternate Methods of Administration
For patients who are unable to swallow the tablet(s) whole, Teva-Ticagrelor tablets (90 mg) can be crushed to a fine powder and mixed in half a glass of water and drunk immediately. The glass should be rinsed with a further half glass of water and the contents drunk. The mixture can also be administered via a nasogastric tube (CH8 or greater). It is important to flush the nasogastric tube through with water after administration of the mixture.
4.5 Missed Dose
Lapses in therapy should be avoided. A patient who misses a dose of Teva-Ticagrelor should take their next dose at its scheduled time (see 10.2 Pharmacodynamics).
5 OVERDOSAGE
Treatment
There is currently no known antidote to reverse the effects of Teva-Ticagrelor (ticagrelor), and ticagrelor is not dialyzable. Treatment of overdose should follow local standard medical practice. The expected effect of excessive Teva-Ticagrelor dosing is prolonged duration of bleeding risk associated with platelet inhibition. If bleeding occurs, appropriate supportive measures should be taken (see General).
Signs and Symptoms
Ticagrelor is well tolerated in single doses up to 900 mg. Gastrointestinal toxicity was dose-limiting in a single ascending dose study. Other clinically meaningful adverse effects which may occur with overdose include dyspnea and ventricular pauses.
Single oral doses of ticagrelor to mice caused no observable effects at doses up to 2000 mg/kg. Single oral doses of 500 and 2000 mg/kg ticagrelor to rats caused a transient reduction in body weight with no other observable effects.
In the event of overdose, observe for these potential adverse effects and consider ECG monitoring.
| For management of a suspected drug overdose, contact your regional poison control centre. |
|---|
6 DOSAGE FORMS, STRENGTHS, COMPOSITION AND PACKAGING
Table 1: Dosage Form, Strengths and Composition
| Route of Administration | Dosage Form / Strength / Composition | Nonmedicinal Ingredients |
| Oral | Tablet 60 mg and 90 mg | Mannitol, anhydrous dibasic calcium phosphate, povidone, sodium starch glycolate, magnesium stearate, hypromellose, titanium dioxide, polyethylene glycol, talc, iron oxide yellow (90 mg), iron oxide red |
Teva-Ticagrelor(ticagrelor) is available as 60 mg film-coated tablets which are light pink to pink colored, round shaped, debossed with"137" on one side and "A" on other side.
Teva-Ticagrelor(ticagrelor) is available as 90 mg film-coated tablets which are light yellow to yellow colored, round shaped, debossed with"A91" on one side and plain on other side.
Packaging
Teva-Ticagrelor 90 mg is available in HDPE bottles of 60 tablets for institutional use only and blister packs of 60 tablets (6 x 10 tablets).
Teva-Ticagrelor 60 mg is available in HDPE bottles of 60 tablets and blister packs of 60 tablets
(6 x 10 tablets).
7 WARNINGS AND PRECAUTIONS
General
Benefit-risk in patients with coronary artery disease (CAD) and type-2 diabetes mellitus (DM): In the THEMIS trial, a positive benefit-risk profile was observed in the pre-specified subgroup of patients who have a history of percutaneous intervention (PCI), representing 58% of the overall THEMIS trial population. In the full THEMIS population, the benefit-risk profile was not considered favourable to support use of ticagrelor. Before initiating treatment in patients with CAD, type-2 diabetes and a history of PCI, it should be confirmed that a patient is at high risk of atherothrombotic events and low risk of bleeding (see 1 INDICATIONS, 8 ADVERSE REACTIONS and 14 CLINICAL TRIALS).
Bleeding Risk: As with other antiplatelet agents, the use of Teva-Ticagrelor in patients at known increased risk for bleeding should be balanced against the benefit in terms of prevention of thrombotic events (see 8 ADVERSE REACTIONS). The treating physician
should regularly reassess whether treatment with Teva-Ticagrelor remains appropriate, particularly if there is a change in the factors associated with an increased risk of bleeding.
If clinically indicated, Teva-Ticagrelor should be used with caution in the following patient groups:
Patients with a propensity to bleed (e.g. due to recent trauma, recent surgery, coagulation disorders, or recent gastrointestinal bleeding). The use of Teva-Ticagrelor
is contraindicated in patients with active pathological bleeding, in those with a history of intracranial hemorrhage, and moderate to severe hepatic impairment (see 2 CONTRAINDICATIONS).
Patients who are at increased risk of trauma. The treating physician should inform
patients of this risk and discuss preventive measures of trauma (see 8 ADVERSE REACTIONS).
Patients requiring oral anticoagulants (e.g. warfarin, see 9 DRUG INTERACTIONS) and/or fibrinolytics agents (within 24 hours of Teva-Ticagrelor dosing). Such agents confer an independent bleeding risk as they function in a distinct and complementary mechanism of hemostasis compared to ticagrelor. The combination of ticagrelor with either of these classes of drugs has not been studied.
- Warfarin Therapy: Due to an increased propensity to bleed, caution is advised in patients taking warfarin during Teva-Ticagrelor therapy. A specific drug-drug interaction study with warfarin has not been performed (see 9 DRUG INTERACTIONS).
- Patients with concomitant administration of medicinal products that may increase the risk of bleeding, e.g. non-steroidal anti-inflammatory drugs (NSAIDs).
Single antiplatelet therapy in patients with ACS who have undergone PCI: Discontinuing ASA after 3 months and continuing with ticagrelor as single antiplatelet therapy has been shown to decrease the risk of bleeding, with no observed increase in risk of major adverse cardiovascular events (MACE), in patients with ACS who have undergone a PCI procedure. Before the decision to discontinue ASA and continue with Teva-Ticagrelor as single antiplatelet therapy, it should be confirmed that a patient is at an increased risk of bleeding. The decision should be based on clinical judgment considering the risk of bleeding versus the risk of thrombotic events in patients with ACS who have undergone PCI.
Platelet transfusion did not reverse the antiplatelet effect of ticagrelor in healthy volunteers and is unlikely to be of clinical benefit in patients with bleeding. Since co-administration of ticagrelor with desmopressin did not decrease template bleeding time, desmopressin is unlikely to be effective in managing clinical bleeding events.
Antifibrinolytic therapy (aminocaproic acid or tranexamic acid) and/or recombinant factor VIIa therapy may augment hemostasis. Teva-Ticagrelor may be resumed after the cause of bleeding has been identified and controlled.
Maintenance Dose Acetylsalicylic Acid (ASA): Based on a relationship observed in PLATO between maintenance ASA dose and relative efficacy of ticagrelor compared to clopidogrel, co-administration of Teva-Ticagrelor and high maintenance dose ASA (> 150 mg daily) is not recommended (see 1 INDICATIONS and 4 DOSAGE AND ADMINISTRATION).
Cytochrome P450 3A4 Strong Inhibitors: Co-administration of Teva-Ticagrelor with strong CYP3A4 inhibitors (e.g. ketoconazole, clarithromycin, nefazodone, ritonavir, and atazanavir) is contraindicated as co-administration may lead to a substantial increase in exposure to ticagrelor (see 8 ADVERSE REACTIONS and 9 DRUG INTERACTIONS).
Premature Discontinuations: Patients who require discontinuation of Teva-Ticagrelor are at increased risk for cardiac events. Premature discontinuation of treatment should be avoided. If Teva-Ticagrelor must be temporarily stopped due to an adverse event, it should be re-initiated as soon as possible when the benefits outweigh the risks of the adverse event or when the adverse event has come to resolution.
Uric Acid Increase: In PLATO, patients on ticagrelor had a higher risk of hyperuricemia than those receiving clopidogrel. In PEGASUS, a greater incidence of gout, gouty arthritis and hyperuricemias was reported in patients on ticagrelor compared to aspirin alone. In THEMIS, there was a higher incidence of hyperuricemia in patients on ticagrelor versus aspirin alone, but the incidence of gout was similar. Caution should be exercised when administering Teva-Ticagrelor
to patients with a history of hyperuricemia or gouty arthritis. As a precautionary measure, the use of Teva-Ticagrelor in patients with uric acid nephropathy is discouraged.
Cardiovascular
Patients at Risk for Bradyarrhythmia: Holter ECG monitoring conducted during clinical trials has shown an increased frequency of mostly asymptomatic ventricular pauses during treatment with ticagrelor compared with clopidogrel. In Phase 3 studies (PLATO, PEGASUS and THEMIS)) evaluating the safety and efficacy of ticagrelor, patients with history of sick sinus syndrome, second and third degree atrioventricular (AV) block or bradycardic-related syncope and not protected with a pacemaker were excluded as they may be at increased risk of developing bradyarrhythmias with ticagrelor. The incidence of bradyarrhythmic events in these studies were reported in a similar frequency for ticagrelor and comparators (i.e., clopidogrel or aspirin alone). Bradyarrhythmic events, including second and third degree AV block, have been reported in the post-marketing setting in patients with or without history of bradyarrhythmia, in most cases, shortly after initiation of treatment with ticagrelor. These events occurred primarily in patients with ACS, where cardiac ischemia and concomitant drugs reducing the heart rate or affecting cardiac conduction are potential confounders. In some cases, the bradyarrhythmic events resolved after ticagrelor specifically was discontinued. Some cases of bradyarrhythmia were severe and the patients required pacing (usually temporary). A meta-analysis of randomized control trials suggests that the risk of bradyarrhythmia with ticagrelor may be dose-dependent and that the increased risk with ticagrelor, relative to comparators, is specific to patients with a history of bradyarrhythmia. Therefore, Teva-Ticagrelor should be used with caution in patients deemed at higher risk for bradyarrhythmia and these patients should be closely monitored during the first few weeks on treatment (see 8 ADVERSE REACTIONS and 14 CLINICAL TRIALS).
In addition, caution should be exercised when administering Teva-Ticagrelor concomitantly with drugs known to induce bradycardia. However, no evidence of clinically significant adverse interactions was observed in the PLATO and the PEGASUS trials during concomitant administration with one or more drugs known to induce bradycardia. In PLATO, 96% of patients took beta blockers, 33% took diltiazem or verapamil (calcium channel blockers), and 4% took digoxin. In THEMIS, 73.8% of patients took beta blockers at study entry.
Driving and Operating Machinery
Effects on Ability to Drive and Use Machines: No studies on the effects of ticagrelor on the ability to drive and use machines have been performed. During treatment with ticagrelor, dizziness, confusion, vertigo and syncope have been reported. Therefore, patients who experience these symptoms should be cautious while driving or using machines (see 8 ADVERSE REACTIONS).
Hematologic
Thrombotic Thrombocytopenic Purpura (TTP): TTP has been reported very rarely with the use of ticagrelor. TTP is a serious, potentially fatal condition and requires prompt treatment, plasmapheresis should be considered. TTP is characterized by some or all of the following symptoms and findings; thrombocytopenia, microangiopathic hemolytic anemia (schistocytes seen on peripheral blood smear), neurological findings, renal dysfunction, and fever.
Monitoring and Laboratory Tests
Platelet function tests to diagnose Heparin induced thrombocytopenia (HIT): False negative results in platelet function test for HIT have been reported in patients administered ticagrelor. This is related to inhibition of the P2Y12-receptor on the healthy donor platelets in the test by ticagrelor in the patient’s sera/plasma. Information on concomitant treatment with ticagrelor is required for interpretation of HIT platelet function tests.
Before considering discontinuation of ticagrelor, the benefit and risk of continued treatment should be assessed, taking both the prothrombotic state of HIT and the increased risk of bleeding with concomitant anticoagulant and ticagrelor treatment into consideration.
Neurologic
Central Sleep Apnea: Central sleep apnea including Cheyne-Stokes respiration has been reported in the post-marketing setting in patients taking ticagrelor. If central sleep apnea is suspected, further clinical assessment may be considered.
Patients with Prior Ischemic Stroke: ACS patients with prior ischemic stroke can be treated with ticagrelor 90 mg for up to 12 months (PLATO). In PEGASUS (history of MI ≥ one year) and THEMIS (CAD and type 2 DM) trials, patients with prior ischemic stroke were excluded because previous studies have shown that combination use of antiplatelet agents (not ticagrelor) is associated with increased risks of intracranial hemorrhage. Therefore, in the absence of data, ticagrelor treatment beyond one year in ACS patients with prior ischemic stroke is not recommended. Teva-Ticagrelor treatment in patients with CAD, type 2 diabetes mellitus and prior ischemic stroke is also not recommended.
Peri-Operative Considerations
Surgery: If a patient requires surgery, clinicians should consider each patient's clinical profile as well as the benefits and risks of continued antiplatelet therapy when determining when discontinuation of Teva-Ticagrelor treatment should occur.
In PLATO patients undergoing CABG, ticagrelor had a similar rate of major bleeds compared to clopidogrel at all days after stopping therapy except Day 1 where ticagrelor had a higher rate of major bleeding (see 8 ADVERSE REACTIONS).
Because of the reversible binding of ticagrelor, restoration of platelet aggregation occurs faster with ticagrelor compared to clopidogrel.
In the OFFSET study, mean Inhibition of Platelet Aggregation (IPA) for ticagrelor at 72 hours post-dose was comparable to mean IPA for clopidogrel at 120 hours post-dose. The more rapid offset of effect may predict a reduced risk of bleeding complications, e.g. in settings where antiplatelet therapy must be temporarily discontinued due to surgery or trauma (see 10.2 Pharmacodynamics).
To minimize the risk of bleeding, if a patient is to undergo elective surgery and antiplatelet effect is not desired, Teva-Ticagrelor should be discontinued 5 days prior to surgery.
Renal
Renal Impairment: No dosage adjustment is required in patients with renal impairment. Ticagrelor is not dialyzable. Appropriate caution should be used in patients requiring renal replacement therapy. Creatinine levels may increase during treatment with Teva-Ticagrelor. The mechanism has not been identified. Renal function should be monitored in the course of patient management (see 8 ADVERSE REACTIONS and Special Populations and Conditions).
Respiratory
Dyspnea: In clinical trials, approximately 14% of patients randomized to ticagrelor 90 mg (PLATO) or 60 mg twice daily (PEGASUS) reported dyspnea, including dyspnea at rest, exertional dyspnea, paroxysmal nocturnal dyspnea, and nocturnal dyspnea (see 8 ADVERSE REACTIONS). The patients experienced a single episode in 85% of the cases. The dyspnea is usually mild to moderate in intensity and often resolves during continued ticagrelor treatment.
In the THEMIS trial, approximately 21.4 % of patients randomized to ticagrelor experienced dyspnea events. The characteristics of those dyspnea events in THEMIS are consistent with those described previously (see 8 ADVERSE REACTIONS).
Ticagrelor should be used with caution in older patients and in patients with history of asthma and/or chronic obstructive pulmonary disease. If a patient reports new, prolonged or worsened dyspnea this should be investigated fully and if not tolerated, treatment with Teva-Ticagrelor should be stopped (see 8 ADVERSE REACTIONS). The mechanism has not yet been elucidated.
PLATO data do not suggest that the higher frequency of dyspnea with ticagrelor 90 mg is due to new or worsening heart or lung disease. In patients who underwent pulmonary function testing in the clinical program, there was no indication of an adverse effect of ticagrelor 90 mg on pulmonary function.
7.1 Special Populations
7.1.1 Pregnant Women
The safety of ticagrelor during pregnancy has not been established, as no clinical study has been conducted in pregnant women and limited clinical data on exposure to ticagrelor during pregnancy are available. Women of child bearing potential should use appropriate contraceptive measures to avoid pregnancy.
7.1.2 Breast-feeding
It is not known whether this drug is excreted in human milk, as no clinical study has been conducted in lactating women. Studies in rats have shown that ticagrelor and its active metabolites are excreted in milk (see Special Populations and Conditions). Therefore, the use of Teva-Ticagrelor during breastfeeding is not recommended.
7.1.3 Pediatrics
Pediatrics (< 18 years of age): The safety and efficacy of ticagrelor in pediatric patients below the age of 18 have not been established. In a randomized, double-blind, placebo-controlled, phase 3 trial, in pediatric patients aged 2 to less than 18 years with sickle cell disease, the primary objective of reducing the rate of vaso-occlusive crises was not met. Teva-Ticagrelor should not be used in pediatric patients with sickle cell disease. Therefore, Health Canada has not authorized an indication for pediatric use. See 1.1 Pediatrics.
7.1.4 Geriatrics
Geriatrics (≥ 65 years of age): No overall differences in safety or efficacy were observed in geriatric patients in the PLATO, PEGASUS and THEMIS trials (see 1 INDICATIONS and 14 CLINICAL TRIALS), and no dosage adjustment is required in elderly (≥ 65 years) patients (see 4 DOSAGE AND ADMINISTRATION).
8 ADVERSE REACTIONS
8.1 Adverse Reaction Overview
The safety profile of ticagrelor has been evaluated in three large randomized phase 3 outcome trials (PLATO, PEGASUS and THEMIS) including more than 58,000 patients of which more than 32,000 patients were exposed to ticagrelor (see 14 CLINICAL TRIALS).
Acute Coronary Syndrome
In PLATO, a total of 6,762 patients with Acute Coronary Syndromes (UA, NSTEMI and STEMI) were exposed to ticagrelor (180 mg loading dose followed by a 90 mg twice daily maintenance dose) for at least 6 months and up to 12 months for 3,138 of them.
The commonly reported adverse events in patients treated with ticagrelor were dyspnea, headache and epistaxis and these events occurred at higher rates than in the clopidogrel treatment group (see Table 4).
Serious adverse events were reported in a similar frequency between ticagrelor (20.2%) and clopidogrel (20.3%) treated patients. The most frequent serious adverse events observed were cardiac failure (1.1% vs. 1.0%), non-cardiac chest pain (0.9% vs. 0.9%) and dyspnea (0.7% vs. 0.4%).
The rate of study drug discontinuation because of adverse events was 7.4% for ticagrelor and 5.4% for clopidogrel. Dyspnea was the most common adverse events leading to study drug discontinuation for ticagrelor (0.9% for ticagrelor and 0.1% for clopidogrel).
History of Myocardial Infarction (≥One Year)
The safety of ticagrelor in patients with a history of spontaneous MI (MI occurred at least one year ago) and high risk of developing an atherothrombotic event was evaluated in the PEGASUS study, which compared patients treated with ticagrelor 60 mg twice daily (N=6,958) or 90 mg twice daily combined with low dose ASA (75-150 mg) (N=6,988) to low dose ASA (75-150 mg) therapy alone (N=6,996). The ticagrelor 60 mg dose is the only dose approved for this indication. Median treatment duration for ticagrelor 60 mg was 29.4 months (see 14 CLINICAL TRIALS).
The commonly reported adverse events in this patient population on ticagrelor were dyspnea, epistaxis, increased tendency to bruise and contusion, and these events occurred at higher rates with ticagrelor than on ASA alone (see Table 7).
The proportion of patients who had serious adverse events was similar across the treatment groups (21.5% for ticagrelor 60 mg and 21.6% for ASA alone). The most common serious adverse events more frequently reported with ticagrelor were atrial fibrillation, syncope, dyspnea, iron deficiency anemia and epistaxis.
In PEGASUS patients on ticagrelor had a higher incidence of discontinuation due to adverse events compared to ASA alone (16.1% for ticagrelor 60 mg and 8.5% for ASA therapy alone). The most common adverse events leading to study discontinuation reported at higher rates with ticagrelor than on ASA alone were dyspnea, increased tendency to bruise, epistaxis and spontaneous hematoma.
Coronary Artery Disease (CAD) and Type 2 Diabetes Mellitus (DM) with a history of percutaneous coronary intervention (PCI)
The safety of ticagrelor in patients with CAD and type 2 DM who are at high risk of atherothrombotic events was evaluated in the THEMIS study, which compared patients treated with ticagrelor (9,562 patients) or placebo (9,531 patients) twice daily on a background of low dose ASA (75-150 mg). In the subgroup of patients with a history of PCI, 5,536 patients received ticagrelor and 5,564 patients received placebo. Ticagrelor 60 mg is the recommended dose for this indication. Median treatment duration for ticagrelor in the THEMIS trial was 33.2 months (see 14 CLINICAL TRIALS).
Safety was evaluated in THEMIS through assessment of serious adverse events, bleeding events, adverse events of interest (i.e., bradyarrhythmia, dyspnea, gout, pneumonia and renal impairment) and discontinuations due to adverse events.
The proportion of patients who had serious adverse events in the subgroup of THEMIS patients with a history of PCI was similar across the treatment groups (32.2% for ticagrelor in combination with ASA vs. 35.7% for ASA alone). The most commonly reported serious adverse events with similar or higher incidence for ticagrelor compared to ASA alone were acute kidney injury (0.5 vs. 0.4%), transient ischaemic attack (0.5 vs. 0.4%), gastrointestinal hemorrhage (0.5% vs. 0.2%) and hematuria (0.4 vs. 0.1%).
In the subgroup of THEMIS patients with a history of PCI, similar rates of adverse events of interest were observed in both treatment groups except for dyspnea. Dyspnea was reported in 22.0% of patients taking ticagrelor in combination with ASA and 7.5% of patients taking ASA alone.
In the subgroup of THEMIS patients with a history of PCI, discontinuation of study drug due to adverse events was higher for ticagrelor (21.3%) in combination with ASA versus ASA alone (13.0%). The most common adverse events leading to study discontinuation reported at higher rates with ticagrelor compared to ASA alone were dyspnea, increased tendency to bruise, epistaxis and ecchymosis.
8.2 Clinical Trial Adverse Reactions
Clinical trials are conducted under very specific conditions. The adverse reaction rates observed in the clinical trials; therefore, may not reflect the rates observed in practice and should not be compared to the rates in the clinical trials of another drug. Adverse reaction information from clinical trials may be useful in identifying and approximating rates of adverse drug reactions in real-world use.
Acute Coronary Syndrome
Bleeding Events
The primary safety endpoint in the PLATO study was the composite endpoint of ‘Total Major’ bleeding, which consisted of the components of ‘Major Fatal/Life-threatening’ and ‘Major Other’. Table 2 shows the 12 month rates of patients experiencing bleeding events in the PLATO study (PLATO defined).
| Table 2: Analysis of overall bleeding events, Kaplan-Meier estimate of bleeding rates by treatment at 12 months - PLATO-defined | ||||||||
|---|---|---|---|---|---|---|---|---|
Ticagrelor 90 mg twice daily N=9235 (%) | Clopidogrel 75 mg once daily N=9186 (%) | p-value* | ||||||
| Primary Safety Endpoint | ||||||||
| Total Major | 11.6 | 11.2 | 0.4336 | |||||
| Secondary Safety Endpoints | ||||||||
| Major Fatal/Life-Threatening | 5.8 | 5.8 | 0.6988 | |||||
| Combined Total Major + Minor | 16.1 | 14.6 | 0.0084 | |||||
| Non-Procedural Major | 3.1 | 2.3 | 0.0058 | |||||
| Non-Procedural Major + Minor | 5.9 | 4.3 | <0.0001 | |||||
| Non-CABG Total Major | 4.5 | 3.8 | 0.0264 | |||||
| Non-CABG Major Fatal/Life-threatening | 2.1 | 1.9 | 0.2516 | |||||
* Nominal p-value not corrected for multiple testing.
Major Fatal/Life-threatening: Clinically apparent with > 50 g/L decrease in hemoglobin or ≥ 4 red cell units transfused; or fatal; or intracranial; or intrapericardial with cardiac tamponade; or with hypovolemic shock or severe hypotension requiring pressors or surgery.
Major Other: Clinically apparent with 30-50 g/L decrease in hemoglobin or 2-3 red cell units transfused; or significantly disabling.
Minor: Requires medical intervention to stop or treat bleeding.
There were few fatal bleeding events in the study, 20 (0.2%) for ticagrelor 90 mg twice daily and 23 (0.3%) for clopidogrel 75 mg once daily. When minor bleeding was included, combined PLATO-defined Major and Minor bleeding events were significantly higher on ticagrelor than on clopidogrel.
Location of ‘Total Major + Minor’ Bleeding (ticagrelor versus clopidogrel): intracranial 0.3% vs. 0.2%, pericardial 0.1% vs. 0.1%, retroperitoneal 0.03% vs. 0.03%, intraocular 0.02% vs. 0.04% and intra-articular 0.02% vs. 0.01%. Other common locations were in rank order of event frequency: gastrointestinal 1.8% vs. 1.5%, epistaxis 1.3% vs. 0.7%, urinary 0.5% vs. 0.4%, subcutaneous/dermal 0.5% vs. 0.4% and hemoptysis 0.1% vs. 0.08%.
Non-procedural Fatal Bleeding: There was no difference with ticagrelor compared to clopidogrel for overall non-procedural fatal bleeding. There were numerically more ‘Major Fatal/Life-threatening’ intracranial non-procedural bleeding events with ticagrelor (n=27 events, 0.3%) than with clopidogrel (n=14 events, 0.2%). Of the intracranial non-procedural bleeding events, 11 bleeding events with ticagrelor and 1 with clopidogrel were fatal. ‘Major Fatal/Life-threatening’ gastrointestinal bleeding was the same with ticagrelor and clopidogrel, with numerically more fatal events for clopidogrel (5) than for ticagrelor (none).
Bleeding in Patient Subpopulations: Baseline characteristics including age, gender, weight, race, geographic region, medical history, concurrent conditions and concomitant therapy were assessed to explore any increase in risk of bleeding with ticagrelor. No particular risk group was identified for any subset of bleeding.
Table 3 shows the overall rates of TIMI-defined bleeding events.
| Table 3: Analysis of overall bleeding events - TIMI-defined | |||||
|---|---|---|---|---|---|
Ticagrelor N=9235 (%) | Clopidogrel N=9186 (%) | p-value | |||
| Major | 7.9 | 7.7 | 0.5669 | ||
| Major + Minor | 11.4 | 10.9 | 0.3272 | ||
| Non-CABG Major | 2.8 | 2.2 | 0.0246 | ||
| Non-CABG Major + Minor | 4.5 | 3.6 | 0.0093 | ||
TIMI Major: Clinically apparent with > 50 g/L decrease in hemoglobin or intracranial hemorrhage.
TIMI Minor: Clinically apparent with 30 to ≤ 50 g/L decrease in hemoglobin.
Other Adverse Events
The incidence of adverse events (regardless of causality) reported for ≥ 1% of patients treated with ticagrelor and clopidogrel in the PLATO study are presented in Table 4.
| Table 4: Summary of adverse events (regardless of causality) reported for ≥ 1% of patients in either group (PLATO) | |||||
|---|---|---|---|---|---|
| Adverse Event (System Organ Class) | Ticagrelor N=9235 (%) | Clopidogrel N=9186 (%) | |||
| Blood and Lymphatic System Disorders | |||||
| Anemia | 1.9 | 1.7 | |||
| Cardiac Disorders | |||||
| Table 4: Summary of adverse events (regardless of causality) reported for ≥ 1% of patients in either group (PLATO) | |||||
|---|---|---|---|---|---|
| Adverse Event (System Organ Class) | Ticagrelor N=9235 (%) | Clopidogrel N=9186 (%) | |||
| Atrial fibrillation | 4.2 | 4.6 | |||
| Bradycardiaa | 2.9 | 2.9 | |||
| Cardiac failure | 2.3 | 2.6 | |||
| Ventricular tachycardia | 2.0 | 2.1 | |||
| Palpitations | 1.2 | 1.1 | |||
| Angina pectoris | 1.2 | 1.1 | |||
| Sinus bradycardia | 1.1 | 0.8 | |||
| Ventricular extrasystoles | 1.1 | 1.1 | |||
| Ventricular fibrillation | 0.8 | 1.0 | |||
| Ear and Labyrinth Disorders | |||||
| Vertigob | 1.5 | 1.3 | |||
| Gastrointestinal Disorders | |||||
| Nauseab | 4.3 | 3.8 | |||
| Diarrheab | 3.7 | 3.3 | |||
| Vomitingb | 2.5 | 2.3 | |||
| Constipationb | 2.2 | 2.6 | |||
| Dyspepsiab | 2.0 | 1.8 | |||
| Abdominal pain upper | 1.9 | 2.0 | |||
| Abdominal painb | 1.5 | 1.2 | |||
| General Disorders and Administration Site Conditions | |||||
| Non-cardiac chest pain | 3.7 | 3.3 | |||
| Fatigue | 3.2 | 3.2 | |||
| Chest pain | 3.1 | 3.5 | |||
| Pyrexia | 2.9 | 2.8 | |||
| Edema peripheral | 2.3 | 2.5 | |||
| Asthenia | 2.0 | 2.1 | |||
| Hemorrhages or bleeding | |||||
| Epistaxisb | 6.0 | 3.4 | |||
| Contusion | 3.9 | 2.0 | |||
| Hematoma | 2.2 | 1.3 | |||
| Post-procedural hemorrhageb | 2.1 | 2.0 | |||
| Vessel puncture site hematoma | 1.7 | 1.1 | |||
| Ecchymosis | 1.5 | 0.6 | |||
| Infections and Infestations | |||||
| Urinary tract infection | 2.0 | 1.8 | |||
| Hematuria | 1.9 | 1.6 | |||
| Nasopharyngitis | 1.8 | 1.6 | |||
| Pneumonia | 1.4 | 1.9 | |||
| Bronchitis | 1.3 | 1.4 | |||
| Metabolism and Nutrition Disorders | |||||
| Table 4: Summary of adverse events (regardless of causality) reported for ≥ 1% of patients in either group (PLATO) | |||||
|---|---|---|---|---|---|
| Adverse Event (System Organ Class) | Ticagrelor N=9235 (%) | Clopidogrel N=9186 (%) | |||
| Diabetes mellitus | 1.2 | 1.1 | |||
| Dyslipidaemia | 1.0 | 1.0 | |||
| Hypercholesterolaemia | 1.0 | 0.9 | |||
| Hypokalaemia | 1.6 | 1.5 | |||
| Musculoskeletal and Connective Tissue Disorders | |||||
| Back pain | 3.6 | 3.3 | |||
| Pain in extremity | 2.1 | 2.3 | |||
| Musculoskeletal chest pain | 1.5 | 1.4 | |||
| Musculoskeletal pain | 1.5 | 1.5 | |||
| Arthralgia | 1.5 | 1.4 | |||
| Myalgia | 1.4 | 1.6 | |||
| Nervous System Disorders | |||||
| Headache | 6.5 | 5.8 | |||
| Dizziness | 4.5 | 3.9 | |||
| Syncope | 1.1 | 0.8 | |||
| Psychiatric Disorders | |||||
| Anxiety | 2.2 | 1.9 | |||
| Insomnia | 1.7 | 2.0 | |||
| Depression | 1.1 | 1.1 | |||
| Renal and Urinary Disorders | |||||
| Renal failure | 1.0 | 0.7 | |||
| Respiratory Disorders | |||||
| Dyspneaa, b | 12.0 | 6.5 | |||
| Cough | 4.9 | 4.6 | |||
| Dyspnea Exertional | 1.9 | 1.4 | |||
| Skin and Subcutaneous Tissue Disorders | |||||
| Rashb | 1.8 | 1.7 | |||
| Pruritusb | 1.0 | 1.0 | |||
| Vascular Disorders | |||||
| Hypertension | 3.8 | 4.0 | |||
| Hypotension | 3.2 | 3.3 | |||
- a. Several MedDRA PT combined.
- b. These events have also been reported as Adverse Drug Reactions (possibly or probably related to ticagrelor).
Additional clinical Adverse Drug Reactions that were reported as possibly or probably related to ticagrelor are listed below by body system:
Common (≥ 1% to < 10%)
- Skin and subcutaneous tissue disorders: subcutaneous or dermal bleeding
- Gastrointestinal disorders: gastrointestinal hemorrhages
- Renal and urinary disorders: urinary tract bleeding
History of Myocardial Infarction (≥One Year)
Bleeding Events
The primary safety endpoint in the PEGASUS study was the ‘TIMI Major bleeding’. The safety analysis included: time to first TIMI Major bleeding event following the first dose of study drug, time to first TIMI Major or Minor bleeding event and time to first PLATO Major bleeding event.
Table 5 shows the 36-month rates of patients experiencing bleeding events in the ‘on treatment’ analysis of the PEGASUS study (TIMI defined).
| Table 5: Analysis of overall bleeding events, Kaplan-Meier estimate of bleeding rates by treatment at 36 months (PEGASUS) - TIMI-defined | ||||||
|---|---|---|---|---|---|---|
Ticagrelor 60 mg twice daily with ASA N=6958 (%) | ASA alone N=6996 (%) | p-value | ||||
| Primary Safety Endpoint | ||||||
| TIMI Major bleeding* | 2.3 | 1.1 | <0.0001 | |||
| Other Safety Endpoints | ||||||
| Fatal | 0.3 | 0.3 | 1.0000 | |||
| ICH | 0.6 | 0.5 | 0.3130 | |||
| Other Major | 1.6 | 0.5 | <0.0001 | |||
| TIMI Major or Minor | 3.4 | 1.4 | <0.0001 | |||
| TIMI Major or Minor or Requiring medical attention | 16.6 | 7.0 | <0.0001 | |||
*TIMI Major: Fatal bleeding OR any intracranial bleeding OR clinically overt signs of hemorrhage associated with a drop in hemoglobin (Hgb) of ≥50 g/L, or when Hgb is not available, a fall in hematocrit (Hct) ≥15%.
Fatal: A bleeding event that directly led to death within 7 days.
ICH: Intracranial hemorrhage.
Other TIMI Major: Non-fatal non-ICH TIMI Major bleeding.
TIMI Minor: Clinically apparent with 30 to <50 g/L decrease in hemaglobin, or when Hgb is not available, a fall in hematocrit (Hct) of 9 to <15%.
TIMI Requiring medical attention: Requiring intervention, OR leading to hospitalization, OR prompting evaluation.
In PEGASUS, TIMI Major bleeding for ticagrelor 60 mg twice daily was higher than for ASA alone. No increased bleeding risk was seen for fatal bleeding and a small increase was observed in intracranial haemorrhages, as compared to ASA therapy alone. The number of fatal bleeding events in the study was, 11 (0.3%) for ticagrelor 60 mg and 12 (0.3%) for ASA therapy alone and most of these events involved cases of intracranial and gastrointestinal bleedings. The observed increased risk of TIMI Major bleeding with ticagrelor 60 mg was primarily due to a higher frequency of Other TIMI Major bleeding driven by events in the system organ class (SOC) gastrointestinal disorders; and injury, poisoning and procedural complications. The majority of TIMI major bleeding was reported as spontaneous.
Increased bleeding patterns similar to TIMI Major were seen for TIMI Major or Minor (see Table 5) and PLATO-defined Major and PLATO-defined Major or Minor bleeding categories (see Table 6). Discontinuation of treatment due to bleeding was more common with ticagrelor 60 mg compared to ASA therapy alone (6.2% and 1.5%, respectively). The majority of these bleedings were classified as TIMI Requiring medical attention, e.g. epistaxis, bruising and spontaneous hematomas. The most common causes of discontinuation due to a TIMI major bleeding event were gastrointestinal and traumatic intracranial hemorrhage.
Table 6 shows the overall rates of PLATO-defined bleeding events.
| Table 6: Analysis of overall bleeding events -PLATO-defined | ||||||
|---|---|---|---|---|---|---|
Ticagrelor 60 mg bd N=6958 (%) | ASA alone N=6996 (%) | p-value | ||||
| PLATO Major bleeding* | 3.5 | 1.4 | <0.0001 | |||
| Fatal/life-threatening | 2.4 | 1.1 | <0.0001 | |||
| Other PLATO Major | 1.1 | 0.3 | <0.0001 | |||
| PLATO Major or Minor | 15.2 | 6.2 | <0.0001 | |||
*PLATO Major Fatal/life-threatening: Fatal bleeding, OR any intracranial bleeding, OR intrapericardial with cardiac tamponade, OR with hypovolemic shock or severe hypotension requiring pressors/inotropes or surgery OR clinically apparent with ≥50 g/L decrease in hemoglobin or when Hgb is not available, a fall in hematocrit (Hct) ≥15%) OR ≥4 red cell units transfused.
PLATO Major Other: Significantly disabling, OR clinically apparent with 30 to <50 g/L decrease in hemoglobin (or when Hgb is not available, a fall in hematocrit (Hct) of 9 to <15%), OR 2-3 red cell units transfused.
PLATO Minor: Requires medical intervention to stop or treat bleeding.
Intracranial bleeding: Spontaneous ICHs were reported in similar rates for ticagrelor 60 mg and ASA therapy alone (0.2% in both treatment groups). Traumatic and procedural ICHs showed an increase with ticagrelor 60 mg treatment, (n=15, 0.2%) compared with ASA therapy alone (n=10, 0.1%). There were 6 fatal ICHs with ticagrelor 60 mg and 5 with ASA therapy alone.
Bleeding in Patient Subpopulations: The bleeding profile of ticagrelor 60 mg was generally consistent across multiple pre-defined subgroups (e.g. by age, gender, weight, ethnicity, geographic region, concurrent conditions, concomitant therapy, and medical history) for TIMI Major, TIMI Major or Minor and PLATO Major Bleeding events.
Common Bleeding Adverse Drug Reactions (≥1% to <10%) with ticagrelor by body system:
Blood and lymphatic system disorders: blood disorder bleedings (increased tendency to bruise, spontaneous hematoma, hemorrhagic diathesis)
Gastrointestinal disorders: gastrointestinal hemorrhages (gingival, rectal, hemorrhoidal, gastrointestinal ulcer)
Injury, poisoning and procedural complications: post procedural hemorrhage, traumatic bleedings
Respiratory, thoracic and mediastinal disorders: respiratory system bleedings (epistaxis, hemoptysis)
Renal and urinary disorders: urinary tract bleeding (hematuria, cystitis hemorrhage)
Skin and subcutaneous tissue disorders: subcutaneous or dermal bleeding (ecchymosis, skin hemorrhage, petechiae)
Other Adverse Events
The incidence of adverse events (regardless of causality) reported for ≥ 1% of patients treated with ticagrelor 60 mg combined with ASA or ASA alone in the PEGASUS study are presented in Table 7.
| Table 7: Summary of adverse events (regardless of causality) reported for ≥ 1% of patients in the different treatment groups and at a greater incidence with ticagrelor combined with ASA than ASA alone (PEGASUS) | |||||
|---|---|---|---|---|---|
| Adverse Event (System Organ Class) | Ticagrelor 60 mg N=6958 (%) | Placebo - ASA alone N=6996 (%) | |||
| Blood and Lymphatic System Disorders | |||||
| Increased tendency to bruiseb | 6.0 | 0.9 | |||
| Spontaneous hematomab | 3.1 | 0.6 | |||
| Cardiac Disorders | |||||
| Atrial fibrillation | 2.8 | 2.5 | |||
| Palpitations | 1.0 | 0.9 | |||
| Ear and Labyrinth Disorders | |||||
| Vertigob | 1.1 | 1.0 | |||
| Gastrointestinal Disorders | |||||
| Diarrheab | 3.3 | 2.5 | |||
| Nauseab | 2.1 | 1.9 | |||
| Dyspepsia | 1.8 | 1.8 | |||
| Abdominal pain | 1.3 | 1.2 | |||
| Infections and Infestations | |||||
| Bronchitis | 2.7 | 2.6 | |||
| Urinary tract infection | 2.1 | 1.9 | |||
| Sinusitis | 1.1 | 1.0 | |||
| Injury, Poisoning and Procedural Complications | |||||
| Contusionb | 5.0 | 1.5 | |||
| Traumatic hematomab | 2.3 | 0.6 | |||
| Fall | 1.1 | 1.0 | |||
| Investigations | |||||
| Table 7: Summary of adverse events (regardless of causality) reported for ≥ 1% of patients in the different treatment groups and at a greater incidence with ticagrelor combined with ASA than ASA alone (PEGASUS) | |||||
|---|---|---|---|---|---|
| Adverse Event (System Organ Class) | Ticagrelor 60 mg N=6958 (%) | Placebo - ASA alone N=6996 (%) | |||
| Blood pressure increased | 1.0 | 0.8 | |||
| Metabolism and Nutrition Disorders | |||||
| Gout/gouty arthritis/gouty tophusb | 1.5 | 1.1 | |||
| Nervous System Disorders | |||||
| Dizzinessb | 4.2 | 3.7 | |||
| Syncopeb | 1.2 | 0.9 | |||
| Psychiatric Disorders | |||||
| Anxiety | 1.4 | 1.2 | |||
| Insomnia | 1.2 | 1.0 | |||
| Renal and Urinary Disorders | |||||
| Hematuriab | 2.2 | 1.1 | |||
| Reproductive System and Breast Disorders | |||||
| Benign prostatic hyperplasia | 1.4 | 1.3 | |||
| Respiratory, Thoracic and Mediastinal Disorders | |||||
| Dyspneaa,b | 14.4 | 5.5 | |||
| Epistaxisb | 6.1 | 2.2 | |||
| Cough | 2.8 | 2.5 | |||
| Skin and Subcutaneous Tissue Disorders | |||||
| Ecchymosisb | 1.5 | 0.2 | |||
| Pruritusb | 1.0 | 0.9 | |||
| Vascular Disorders | |||||
| Hypotension | 1.4 | 1.0 | |||
- a. includes events of dyspnea, dyspnea exertional and dyspnea at rest.
- b. These events have also been reported as Adverse Drug Reactions (possibly or probably related to ticagrelor).
Coronary Artery Disease (CAD) and Type 2 Diabetes Mellitus (DM) with a history of percutaneous coronary intervention (PCI)
Bleeding Events
The primary safety endpoint in the THEMIS study was the ‘TIMI Major Bleeding’ events. The safety analysis included also the PLATO and BARC bleeding classifications.
In the THEMIS trial, the rate of TIMI Major bleeding was higher for ticagrelor twice daily than for ASA alone (Kaplan-Meier estimate at 36 months: 2.2% vs. 1.2%, respectively, p <0.0001). This higher incidence was characterized by a greater number of fatal bleedings (17 for ticagrelor vs. 10 for ASA) and intracranial hemorrhages (70 for ticagrelor vs. 46 for ASA alone). Most of the intracranial hemorrhages reported in the ticagrelor treatment arm were traumatic events (N=41), most commonly reported in subdural location (see 7 WARNINGS AND PRECAUTIONS).
In the subgroup of patients with a history of PCI, the incidence of TIMI Major bleeding was also higher for ticagrelor compared to ASA alone (Table 8). There were few fatal bleeding events, 6 for ticagrelor in combination with ASA and 6 for ASA therapy alone. The number of patients with intracranial hemorrhages was 33 for ticagrelor in combination with ASA and 31 for ASA alone, corresponding to KM percentages of 0.7% and 0.6%, respectively, p=0.4545. The rate of fatal bleeding and intracranial hemorrhage was however similar in both treatment arms. Among the cases of ICH reported with ticagrelor, 23 were traumatic and 10 were spontaneous. The observed increased risk of TIMI Major bleeding with ticagrelor was therefore primarily due to a higher frequency of events within the system organ class (SOC) gastrointestinal disorders; and injury, poisoning and procedural complications.
Table 8: Analysis of bleeding events, Kaplan-Meier estimate of bleeding rates by treatment at 36 months in the THEMIS subgroup of patients with a history of PCI (“on treatment analysis”)
| Safety Endpoints | Ticagrelor twice daily with ASA N=5536 KM% | ASA alone N=5564 KM% | Hazard Ratio (95% CI) | p-value |
|---|---|---|---|---|
| TIMI-defined bleeding categories | ||||
| TIMI Major | 2.4% | 1.3% | 2.03 (1.48, 2.76) | <0.0001 |
| TIMI Major or Minor | 3.4% | 1.7% | 2.23 (1.70, 2.92) | <0.0001 |
| TIMI Major or Minor or Requiring medical attention | 13.1% | 6.3% | 2.28 (1.99, 2.62) | <0.0001 |
| PLATO-defined bleeding categories | ||||
| PLATO Major | 3.8% | 1.9% | 2.22 (1.72, 2.86) | <0.0001 |
| Fatal/Life-threatening | 2.5% | 1.3% | 2.10 (1.54, 2.86) | <0.0001 |
| Other PLATO Major | 1.5% | 0.6% | 2.53 (1.64, 3.93) | <0.0001 |
Bleeding category definitions:
TIMI Major: Fatal bleeding, OR any intracranial bleeding, OR clinically overt signs of hemorrhage associated with a drop in hemoglobin (Hgb) of ≥50 g/L, or when Hgb is not available, a fall in hematocrit (Hct) of 15%.
If CABG related bleeding: fatal bleeding or perioperative intracranial bleeding or reoperation following closure of the sternotomy incision for the purpose of controlling bleeding or transfusion of ≥5 units of whole blood or PRBCs within a 48 hour period (cell saver transfusion was not counted in calculations of blood products) or chest tube output >2 L within a 24 hour period.
TIMI Minor: Clinically apparent with 30-50 g/L decrease in Hgb or ≥10% to <15% decrease in Hct, OR if no observed blood loss; ≥40 g/L decrease in Hgb concentration or ≥12% decrease in Hct.
TIMI Requiring medical attention: Requiring intervention, OR leading to hospitalization, OR prompting evaluation.
PLATO Major Fatal/life-threatening: Fatal bleeding, OR any intracranial bleeding, OR intrapericardial with cardiac tamponade, OR with hypovolaemic shock or severe hypotension requiring pressors/inotropes or surgery OR clinically apparent with >50 g/L decrease in Hgb OR ≥4 red cell units transfused.
Discontinuation of study drug due to bleeding events in patients with a history of PCI was more common with ticagrelor compared to ASA alone (4.7% and 1.3%, respectively). Epistaxis and increased tendency to bruise were the most common bleeding events resulting in the discontinuation of ticagrelor treatment.
Bleeding in Patient Subpopulations: The bleeding profile of ticagrelor was generally consistent across multiple pre-defined subgroups (e.g., by age, gender, weight, ethnicity, geographic region, concurrent conditions, concomitant therapy, and medical history).
Other Adverse Events: In the THEMIS study protocol, adverse event collection was limited to serious adverse events, discontinuations due to adverse events and adverse events of interest. Adverse event data collected in the THEMIS trial appears consistent with data from PLATO and PEGASUS trials.
8.3 Less Common Clinical Trial Adverse Reactions
Acute Coronary Syndrome
Uncommon (≥ 0.1% to < 1%)
Eye disorders: eye hemorrhage (intraocular, conjunctival, retinal)
Gastrointestinal disorders: gastritis, retroperitoneal hemorrhage
Nervous system disorders: intracranial hemorrhage (may be fatal or life threatening), confusion, paraesthesia
Respiratory, thoracic and mediastinal disorders: hemoptysis
Rare (≥ 0.01% to < 0.1%)
Musculoskeletal connective tissue and bone: hemarthrosis
History of Myocardial Infarction (≥ One Year)
Blood and lymphatic system disorders: anemia
Ear and labyrinth disorders: ear hemorrhage
Eye disorders: eye hemorrhage (intraocular, conjunctival, retinal)
Gastrointestinal disorders: gastritis erosive
Musculoskeletal connective tissue and bone: muscular bleedings (hemarthrosis, muscle hemorrhage)
Neoplasms benign, malignant and unspecified (including cysts and polyps): Tumour bleedings (bleeding from bladder cancer, gastric cancer, colon cancer)
Nervous system disorders: intracranial hemorrhage (may be fatal or life threatening), loss of consciousness
Psychiatric disorders: confusion
Renal and urinary disorders: nephrolithiasis and urinary calculus (bladder, ureteric, urethral)
Reproductive system and breast disorders: reproductive system bleedings (vaginal hemorrhage, hematospermia, postmenopausal hemorrhage)
Respiratory, thoracic and mediastinal disorders: pulmonary fibrosis, pulmonary hypertension
Skin and subcutaneous tissue disorders: purpura
8.4 Abnormal Laboratory Findings: Hematologic, Clinical Chemistry and Other Quantitative Data
Acute Coronary Syndrome
Table 9: Number (%) of patients with blood creatinine increased and hyperuricemia (PLATO)
| Number (%) of patients | ||||||
|---|---|---|---|---|---|---|
| Abnormal Clinical Chemistry Findings | Ticagrelor 90 mg bd (N=9235) | Clopidogrel 75 mg od (N=9186) | ||||
| Blood creatinine increaseda | 335 (8.3%) | 271 (6.7%) | ||||
| Hyperuricemiab | 889 (22.1%) | 537 (13.3%) | ||||
Derived from lab observations.
- a. creatinine increased: >50% from baseline in patients with lab data [ticagrelor 90 mg bd (N=4031); clopidogrel 75 mg od (N=4035)]
- b. hyperuricemia: uric acid increase from ≤ ULN at baseline to > ULN in patients with lab data [ticagrelor 90 mg bd (N=4031); clopidogrel 75 mg od (N=4035)]
Upper limit normal (ULN), provided by central lab, is:
8.0 mg/dl for male (age ≤90), 8.3 mg/dl for male (age >90)
6.9 mg/dl for female (age ≤65), 7.3 mg/dl for female (age 66-90), 7.7 mg/dl for female (age >90)
History of Myocardial Infarction (≥ One Year)
Table 10: Number (%) of patients with blood creatinine increased, hyperuricemia and hemoglobin decreased (PEGASUS)
| Number (%) of patients | |||||
|---|---|---|---|---|---|
| Abnormal Clinical Chemistry Findings | Ticagrelor 60 mg bd (N=6958) | ASA alone (N=6996) | |||
| Blood creatinine increaseda | 243 (3.9%) | 234 (3.6%) | |||
| Hyperuricemiab | 444 (9.1%) | 296 (5.7%) | |||
| Hemoglobin decreasedc | 637 (11.4%) | 460 (7.7%) | |||
Derived from lab observations.
- a. creatinine increased: >50% from baseline in patients with lab data [ticagrelor 60 mg (N=6240); ASA alone (N=6543)]
- b. hyperuricemia: uric acid increase from ≤ ULN at baseline to > ULN in patients with lab data [ticagrelor 60 mg (N=4857); ASA alone (N=5229)]
Upper limit normal (ULN), provided by central lab, is:
8.0 mg/dl for male (age ≤90), 8.3 mg/dl for male (age >90)
6.9 mg/dl for female (age ≤65), 7.3 mg/dl for female (age 66-90), 7.7 mg/dl for female (age >90)
- c. ≥ LLN at baseline and any on-treatment value < LLN: the denominator is patients with hemoglobin at baseline and at least one on-treatment [ticagrelor 60 mg (N=5595); ASA alone (N=5976)]
Lower limit normal (LLN), provided by central lab is:
130 g/L for male (age ≤65); 126 g/L for male (age >65)
116 g/L for female (age ≤65); 110 g/L for female (age >65)
Patients with CAD, Type 2 Diabetes Mellitus and History of PCI
Collection of laboratory data during the randomized treatment period was not part of the THEMIS study protocol, and therefore the table presenting clinically significant changes in laboratory findings is not presented for the patients with CAD, Type 2 Diabetes Mellitus and History of PCI.
8.5 Post-Market Adverse Reactions
The following adverse reactions have been identified during post-approval use of ticagrelor. Because these reactions are reported voluntarily from a population of an unknown size, it is not always possible to reliably estimate their frequency.
Blood disorders: Thrombotic Thrombocytopenic Purpura (see Hematologic)
Cardiac disorders: Bradyarrhythmia, second degree AV block, third degree AV block (see Cardiovascular).
Immune system disorders: hypersensitivity reactions, including angioedema (see 2 CONTRAINDICATIONS)
Nervous system disorders: Central sleep apnea including Cheyne-Stokes respiration (see Neurologic)
Skin and subcutaneous tissue disorders: urticaria, rash
9 DRUG INTERACTIONS
9.1 Serious Drug Interactions
Serious Drug Interactions
|
|---|
9.2 Drug Interactions Overview
Cytochrome P450 (CYP) 3A4/5 are the major enzymes responsible for the metabolism of ticagrelor and the formation of the active metabolite. Clinical pharmacology and in vitro data show that there is a complex interaction between ticagrelor and CYP3A4/5. Indeed, depending on the substrate, ticagrelor and its active metabolite are shown to weakly inhibit or weakly activate CYP3A4/5 (see 10.3 Pharmacokinetics). CYP enzymes 1A2, 2C19, and 2E1 do not contribute meaningfully in vitro to ticagrelor metabolism. Ticagrelor is also a p-glycoprotein (P-gp) substrate and a weak inhibitor of P-gp. Ticagrelor has also been shown to inhibit breast cancer resistant protein (BCRP) in vitro.
9.3 Drug-Behavioural Interactions
Interactions with behaviour have not been studied.
9.4 Drug-Drug Interactions
The drugs listed in this table are based on either drug interaction case reports or studies, or potential interactions due to the expected magnitude and seriousness of the interaction (i.e., those identified as contraindicated).
| Table 11: Established or Potential Drug-Drug Interactions | ||||||
|---|---|---|---|---|---|---|
| Proper Name | Source of Evidence | Effect | Clinical Comment | |||
| Ketoconazole, a strong CYP3A4 inhibitor | CT | Co-administration of ketoconazole with ticagrelor increased the ticagrelor Cmax and AUC equal to 2.4-fold and 7.3-fold, respectively. The Cmax and AUC of ticagrelor’s active metabolite were reduced by 89% and 56%, respectively. | Other strong inhibitors of CYP3A4 (clarithromycin, nefazodone, ritonavir, and atazanavir) would be expected to have similar effects and are contraindicated with Teva-Ticagrelor (see 2 CONTRAINDICATIONS and General). | |||
| Diltiazem, a moderate CYP3A4 inhibitor | CT | Co-administration of diltiazem with ticagrelor increased the ticagrelor Cmax by 69% and AUC by 174% and decreased its active metabolite Cmax by 38% and AUC was unchanged. There was no effect of ticagrelor on diltiazem plasma levels. | Other moderate CYP3A4 inhibitors (e.g., amprenavir, aprepitant, erythromycin, fluconazole, and verapamil) would be expected to have similar effects. These exposure changes are not considered clinically significant, and therefore, can as well be co- administered with Teva-Ticagrelor. | |||
| Table 11: Established or Potential Drug-Drug Interactions | ||||||
|---|---|---|---|---|---|---|
| Proper Name | Source of Evidence | Effect | Clinical Comment | |||
| CYP3A4 inducers, including Rifampin | CT | Co-administration of rifampin with ticagrelor decreased the ticagrelor Cmax and AUC by 73% and 86%, respectively. The Cmax of its active metabolite was unchanged and the AUC was decreased by 46%. | Other strong CYP3A4 inducers (e.g., phenytoin, carbamazepine and phenobarbital) and potentially also weak to moderate inducers (e.g., dexamethasone) would be expected to decrease the exposure to ticagrelor as well and may result in reduced efficacy of Teva-Ticagrelor. Alternative treatments should be considered. | |||
| Cyclosporine, a P-gp and CYP3A4 inhibitor | CT | Co-administration of cyclosporine (600 mg) with ticagrelor increased ticagrelor Cmax and AUC equal to 2.3-fold and 2.8-fold, respectively. The AUC of the active metabolite of ticagrelor was increased by 32% and Cmax was decreased by 15%. There was no effect of ticagrelor on cyclosporine blood levels. | If the association cannot be avoided, use concomitantly with caution. | |||
| Heparin, enoxaparin, acetylsalicylic acid (ASA) | CT | Co-administration of ticagrelor with heparin, enoxaparin and acetylsalicylic acid (ASA) did not have any effect on ticagrelor or its active metabolite plasma levels. Co-administration of ticagrelor and heparin had no effect on heparin based on activated partial thromboplastin time (aPTT) and activated coagulation time (ACT) assays. Co-administration of ticagrelor and enoxaparin had no effect on enoxaparin based on factor Xa assay. | ||||
| Table 11: Established or Potential Drug-Drug Interactions | ||||||
|---|---|---|---|---|---|---|
| Proper Name | Source of Evidence | Effect | Clinical Comment | |||
| CYP3A4/5 substrates with narrow therapeutic indices | CT | Ticagrelor and its active metabolite have the capacity to weakly inhibit or weakly activate CYP3A4/5. | Co-administration of Teva-Ticagrelor with CYP3A4/5 substrates with narrow therapeutic indices is not recommended. Teva-Ticagrelor treatment should be interrupted and resumed when therapy with the CYP3A4/5 substrate is no longer required. | |||
| Simvastatin | CT | Co-administration of ticagrelor with simvastatin increased the simvastatin Cmax by 81% and AUC by 56% and increased simvastatin acid Cmax by 64% and AUC by 52% with some individual increases equal to 2 to 3 fold. There was no effect of simvastatin on ticagrelor plasma levels. | Consideration of the clinical significance should be given to the magnitude and range of changes on the exposure to patients requiring greater than 40 mg of simvastatin. Teva-Ticagrelor may have a similar effect on lovastatin. | |||
| Atorvastatin | CT | Co-administration of atorvastatin and ticagrelor increased the atorvastatin acid Cmax by 23% and AUC by 36%. Similar increases in AUC and Cmax were observed for all atorvastatin acid metabolites. | These increases are not considered clinically significant. | |||
Rosuvastatin (BCRP substrate) | CT | When co-administered, ticagrelor has been shown to increase rosuvastatin concentrations. | The increase in rosuvastatin concentrations may increase the risk of myopathy including rhabdomyolysis. Consideration should be given to the benefits of prevention of major adverse cardiovascular events by use of rosuvastatin and the risks with increased rosuvastatin plasma concentrations. | |||
| Tolbutamide, a CYP2C9 substrate | CT | Co-administration of ticagrelor with tolbutamide resulted in no change in the plasma levels of either drug. | Ticagrelor is not a CYP2C9 inhibitor and unlikely to alter the metabolism of other drugs metabolized via CYP2C9. | |||
| Table 11: Established or Potential Drug-Drug Interactions | ||||||
|---|---|---|---|---|---|---|
| Proper Name | Source of Evidence | Effect | Clinical Comment | |||
| Warfarin | T | A drug-drug interaction study with warfarin has not been performed. As with other oral antiplatelet therapy, there is a potential for increased risk of bleeding. | Warfarin and Teva-Ticagrelor should be co-administered with caution (see 7 WARNINGS AND PRECAUTIONS, General). | |||
| Oral Contraceptives | CT | Co-administration of ticagrelor and levonorgestrel and ethinyl estradiol increased the ethinyl estradiol exposure by approximately 20% but did not alter the PK of levonorgestrel. | No clinically relevant effect on oral contraceptive efficacy is expected when levonorgestrel and ethinyl estradiol are co-administered with Teva-Ticagrelor | |||
| Digoxin (P-gp Substrate) | CT | Concomitant administration of ticagrelor increased the digoxin Cmax by 75% and AUC by 28%. | Appropriate clinical and/or laboratory monitoring is recommended when giving narrow therapeutic index P-gp-dependent drugs like digoxin concomitantly with Teva-Ticagrelor . | |||
| Morphine | CT | Co-administration of morphine with ticagrelor decreased the ticagrelor AUC by approximately 35%. | Delayed and decreased exposure to oral P2Y12 inhibitors. This interaction may be related to reduced gastrointestinal motility and apply to other opioids. The clinical relevance is unknown, but data indicate the potential for reduced ticagrelor efficacy in patients co-administered ticagrelor and morphine. | |||
Legend: CT = Clinical Trial; T = Theoretical
In clinical studies, ticagrelor was commonly administered with ASA, heparin, low molecular weight heparin, intravenous GpIIb/IIIa inhibitors, proton pump inhibitors, statins, beta-blockers, angiotensin converting enzyme inhibitors and angiotensin receptor blockers as needed for concomitant conditions. These studies did not produce any evidence of clinically significant adverse interactions.
9.5 Drug-Food Interactions
In a study of healthy subjects, ingestion of a high-fat meal had no effect on ticagrelor Cmax or the AUC of the active metabolite, but resulted in a 21% increase in ticagrelor AUC and 22% decrease in the active metabolite Cmax. These changes are considered of minimal clinical significance. Ticagrelor was administered without regard to food in PLATO, PEGASUS, and THEMIS. Therefore, Teva-Ticagrelor may be given with or without food.
Grapefruit Juice Interaction: Ingestion of 600 mL of grapefruit juice for four days was shown to increase ticagrelor Cmax by 65% and AUC by 121% and to decrease its active metabolite Cmax by 45% and AUC by 14%. Elimination half-life of ticagrelor was prolonged from 6.7 to 7.2 h and of its active metabolite from 8.2 to 12 h. These exposure changes, despite slightly delaying the recovery of platelet reactivity, are not expected to substantially increase bleeding risk in most patients. See 7 WARNINGS AND PRECAUTIONS, Peri-Operative Considerations, Surgery for stopping Teva-Ticagrelor and bleeding risk with respect to surgery.
9.6 Drug-Herb Interactions
Interactions with herbal products have not been studied.
9.7 Drug-Laboratory Test Interactions
False negative results in platelet function test for Heparin induced thrombocytopenia (HIT) have been reported in patients administered ticagrelor.
10 CLINICAL PHARMACOLOGY
10.1 Mechanism of Action
Ticagrelor, a member of the chemical class cyclopentyl-triazolo-pyrimidines (CPTP), is an oral, direct acting, selective and reversibly binding P2Y12 receptor antagonist that prevents adenosine diphosphate (ADP)-mediated P2Y12 dependent platelet activation and aggregation. Ticagrelor does not prevent ADP binding but when bound to the P2Y12 receptor prevents ADP-induced signal transduction. Indeed, ticagrelor and its active metabolite AR-C124910XX were shown to similarly displace a specific P2Y12 receptor radioligand from the P2Y12 receptors on the surface of human washed platelets in vitro, with a Ki of 2.0 nM and 2.5_nM, respectively. Ticagrelor concentration-dependently inhibited ADP-induced platelet aggregation in suspensions of human and rat washed platelets. It also inhibited ADP-induced platelet aggregation in human platelet rich plasma as well as in marmoset and human whole blood. The ADP induced platelet aggregation measured ex vivo as well as dynamic arterial thrombosis in the damaged femoral artery were also reduced following i.v. administration of ticagrelor in anaesthetised male Beagle dogs. The major circulating metabolite of ticagrelor, O-deethylated AR-C124910XX, showed pharmacological activity comparable to that of the parent molecule.
Since platelets participate in the initiation and/or evolution of thrombotic complications of atherosclerotic disease, inhibition of platelet function has been shown to reduce the risk of cardiovascular events such as death, myocardial infarction or stroke.
Effects on the adenosine system
There is also evidence that ticagrelor reduces cellular uptake of adenosine and prolongs this nucleotide half-life, thereby increasing local endogenous adenosine levels, via potent, concentration dependent and reversible inhibition of equilibrative nucleoside transporter type I (ENT-1). The affinity of ticagrelor for ENT-1 has been documented to be 41 nM. The main circulating metabolite of ticagrelor, AR C124910XX, that has been reported to have a similar affinity for P2Y12 as ticagrelor, only has weak affinity for ENT-1, 330 nM. Whether the ticagrelor-induced increase in adenosine is clinically relevant to the safety and efficacy of ticagrelor remains to be demonstrated.
Effects on the uric acid uptake
Ticagrelor, AR-C124910 (active metabolite) and AR-C133913 (inactive metabolite) were shown to have an inhibitory effect on the OAT-3-dependent uric acid uptake (Ki: AZD6140: 4.9 mcM; AR-C124910: 16.3 mcM; and AR-C133913: 13.4 mcM). They also have a weak inhibitory effect on the URAT1-mediated uric acid uptake. These results suggest that ticagrelor and its metabolites may interfere with the renal transport of uric acid which is consistent with the observation that patients on ticagrelor had a higher risk of hyperuricemia.
10.2 Pharmacodynamics
Inhibition of platelet aggregation mediated by ticagrelor increases with increasing plasma concentrations of ticagrelor and its active metabolite (AR-C124910XX), until almost complete inhibition is attained. The Inhibition of Platelet Aggregation (IPA) gradually decreases with declining plasma ticagrelor and active metabolite concentrations, as the IPA mediated by ticagrelor is reversible. Since ticagrelor reversibly binds to the P2Y12 receptor, the recovery of platelet function is expected to be dependent on the plasma concentrations of ticagrelor and the active metabolite and not on the replacement of irreversibly inhibited platelets as with thienopyridine antiplatelet agents.
The IPA of ticagrelor is generally independent of factors such as race, hepatic or renal disease or co-administered ASA, heparin and enoxaparin.
Onset of Action
In patients with stable coronary artery disease on ASA, ticagrelor demonstrates a rapid onset of IPA effect (Figure 1). Mean IPA for ticagrelor at 0.5 hours after 180 mg loading dose is about 41%, which is similar to clopidogrel’s (600 mg) maximum effect of 50% observed at 8 hours. Ninety percent of patients had final extent IPA > 70% by 2 hours post dose versus 16% for clopidogrel. Ticagrelor’s maximum IPA effect of approximately 88% is reached at around 2 hours, and the IPA between 87%-89% was maintained from 2-8 hours.
Figure 1: Mean final extent IPA (±SD) following single oral doses of 180 mg ticagrelor or 600 mg clopidogrel in patients with stable coronary artery disease
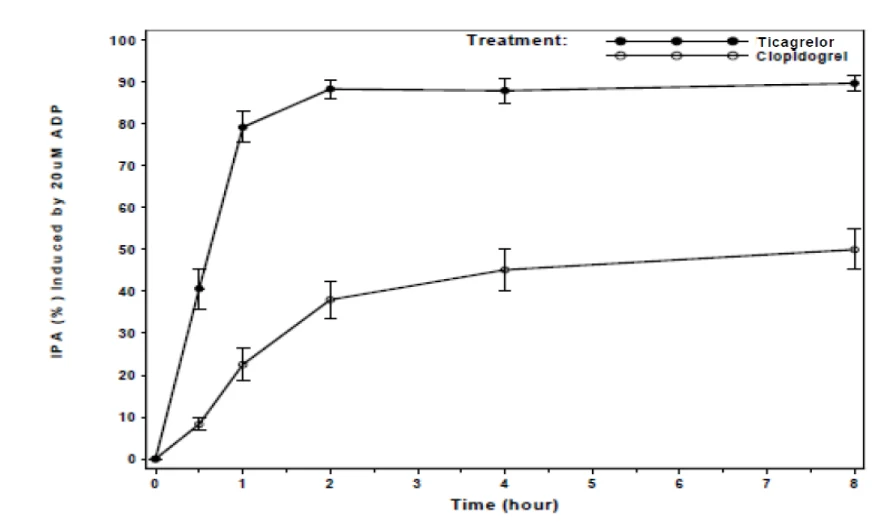
Offset of Effect
After ticagrelor and its active metabolite concentrations decline to a level less than that required for receptor saturation, IPA gradually decreases with declining plasma concentrations. Since ticagrelor binds reversibly, the recovery of platelet function does not depend on replacement of platelets. Ticagrelor has a faster rate of offset of IPA as compared to clopidogrel as determined by the slope of offset from 4-72 hours after last dose (see Peri-Operative Considerations).
Final extent IPA during the 90 mg twice daily-dosing interval is approximately 20%-30% (absolute difference) higher for ticagrelor compared to clopidogrel (75 mg, once daily). However, by 24 hours following the last maintenance dose, the IPA is similar between ticagrelor (58%) and clopidogrel (52%), indicating that patients who miss a dose of ticagrelor would have an IPA level comparable to those treated with once daily clopidogrel (Figure 2).
Figure 2: Mean final extent IPA (±SE) following the last maintenance dose of 90 mg twice daily ticagrelor or 75 mg clopidogrel once daily or placebo
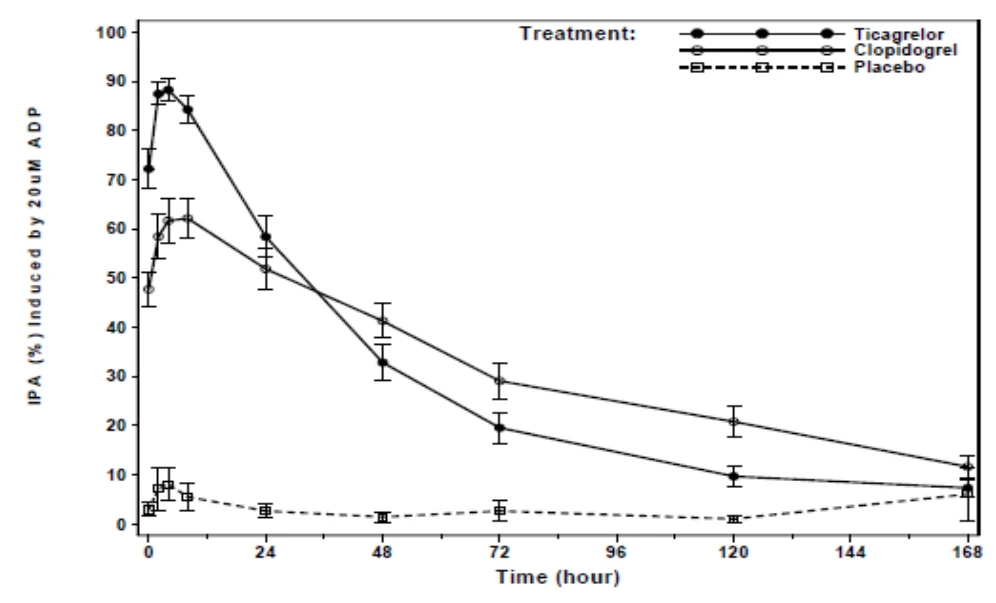
Responders to Ticagrelor
The IPA induced by ticagrelor has less variability with the 90 mg twice daily dose compared to clopidogrel 75 mg once daily. Patients with stable coronary artery disease predetermined to have low IPA response to clopidogrel (non-responders), and given a concomitant dose of ASA, exhibited higher mean IPA response after administration of ticagrelor as compared to clopidogrel.
Switching Data
Switching from clopidogrel 75 mg once daily to ticagrelor 90 mg twice daily results in an absolute IPA increase of 26.4% and switching from ticagrelor to clopidogrel results in an absolute IPA decrease of 24.5%. Patients can be switched from clopidogrel to
Teva-Ticagrelor without interruption of antiplatelet effect (see 4 DOSAGE AND ADMINISTRATION).
10.3 Pharmacokinetics
Ticagrelor demonstrates linear pharmacokinetics. Exposure to ticagrelor and its active metabolite are approximately dose proportional.
The main pharmacokinetic parameters for ticagrelor are presented in the table below.
Table 12: Summary of Ticagrelor Pharmacokinetic Parameters
| Cmax (ng/mL) | Tmax (h) | t½ (h) | AUC0-∞ (ng.h/mL) | CL (L/h)* | Vss (L)* | |
|---|---|---|---|---|---|---|
| Single oral dose mean (90 mg) | 500 | 1.5 | 6.9 | 2233 | 14.2 | 87.5 |
* Following a single intravenous dose of 15 mg ticagrelor
Absorption
Absorption of ticagrelor is rapid with a median Tmax of approximately 1.5 hours. The formation of the major circulating metabolite AR-C124910XX (also active) from ticagrelor is rapid with a median Tmax of approximately 2.5 hours. The Cmax and AUC of ticagrelor and the active metabolite increased in an approximately proportional manner with dose over the dose range studied (30-1260 mg). The pharmacokinetics of ticagrelor and AR-C124910XX in patients with a history of MI (> one year) were generally similar to that in the ACS population. Based on a population pharmacokinetic analysis of the PEGASUS study the median ticagrelor Cmax was 391 ng/ml and AUC was 3801 ng*h/ml at steady state for ticagrelor 60 mg. For ticagrelor 90 mg Cmax was 627 ng/ml and AUC was 6255 ng*h/ml at steady state.
The mean absolute bioavailability of ticagrelor was estimated to be 36%, (range 25.4%-64.0%). In a study of healthy subjects, ingestion of a high-fat meal had no effect on ticagrelor Cmax or the AUC of the active metabolite, but resulted in a 21% increase in ticagrelor AUC and 22% decrease in the active metabolite Cmax. These changes are considered of minimal clinical significance. Ticagrelor was administered without regard to food in PLATO. Therefore,
Teva-Ticagrelor may be given with or without food.
Ticagrelor as crushed tablets mixed in water, given orally or administered through a nasogastric tube into the stomach to 36 healthy volunteers, is bioequivalent to whole tablets. Ticagrelor and the active metabolite (AUC and Cmax are well within the 80-125% range required to demonstrate bioequivalence. Initial exposure (0.5 and 1 hour post-dose) from crushed ticagrelor tablets mixed in water was higher compared to whole tablets, with a generally identical concentration profile thereafter (2 to 48 hours).
Distribution
The steady state volume of distribution of ticagrelor is 87.5 L. Ticagrelor and the active metabolite are extensively bound to human plasma proteins (> 99%).
Ticagrelor was found to be widely distributed in rat tissues and the major organs identified were those associated with metabolism and excretion (liver, pancreas and kidney) as well as glandular tissues (adrenal and pituitary glands), but no accumulation seemed to occur.
Metabolism
The major metabolite of ticagrelor is AR-C124910XX, which is also active as assessed by in vitro binding to the platelet P2Y12 ADP-receptor. The systemic exposure to the active metabolite is approximately 30-40% of that obtained for ticagrelor.
CYP3A is the major enzyme responsible for ticagrelor metabolism and the formation of the active metabolite and their interactions with other CYP3A substrates ranges from activation through to inhibition. Ticagrelor and the active metabolite are weak p-glycoprotein inhibitors.
There is a complex interaction between ticagrelor and CYP3A4/5, depending on the substrate used. In vitro, ticagrelor weakly inhibits testosterone 6ß-hydroxylation, moderately inhibits midazolam 4-hydroxylation and weakly activates nifedipine oxidation and midazolam 1-hydroxylation. Ticagrelor is a BCRP inhibitor in vitro.
Elimination
The primary route of ticagrelor elimination is via hepatic metabolism. When radiolabelled ticagrelor is administered, the mean recovery of radioactivity is approximately 84% (57.8% in feces, 26.5% in urine). Recoveries of ticagrelor and the active metabolite in urine were both less than 1% of the dose. The primary route of elimination for the active metabolite is most likely via biliary secretion. The mean t1/2 was approximately 6.9 hours (range 4.5-12.8 hours) for ticagrelor and 8.6 hours (range 6.5-12.8 hours) for the active metabolite.
Special Populations and Conditions
Pediatrics (< 18 years of age): The safety and efficacy of ticagrelor in pediatric patients below the age of 18 have not been established. In a randomized, double-blind, placebo-controlled, phase 3 trial in pediatric patients aged 2 to less than 18 years with sickle cell disease, treatment with ticagrelor did not show benefit in reducing the rate of vaso-occlusive crises. Teva-Ticagrelor should not be used in pediatric patients with sickle cell disease. Therefore, Health Canada has not authorized an indication for pediatric use. See 1.1 Pediatrics.
- Geriatrics (≥ 65 years of age): Higher exposures to ticagrelor (approximately 60% for both Cmax and AUC) and the active metabolite (approximately 50% for both Cmax and AUC) were observed in elderly (≥ 65 years) subjects compared to younger (18-45 years) subjects. These differences are not considered clinically significant. No dose adjustment is needed for elderly patients (see 7.1 Special Populations and Dosing Considerations in Special Populations).
- Sex: Higher exposures to ticagrelor (approximately 52% and 37% for Cmax and AUC, respectively) and the active metabolite (approximately 50% for both Cmax and AUC) were observed in women compared to men. These differences are not considered clinically significant.
Pregnancy and Breast-feeding: A study performed with pregnant female rats, demonstrated that peak placental concentrations of ticagrelor after i.v. administration were noted at 5 min post-dose, but no significant transfer to the fetus was observed. Moreover, following oral administration of ticagrelor in lactating rats, the maximum milk concentration of ticagrelor and/or its metabolites were found at 4 h post-dose. The observation that the mean concentration in milk was higher than in maternal plasma at all time-points indicates that ticagrelor and its metabolites are easily transferred into milk. The analysis of suckling young animals suggests that these molecules were well absorbed and widely distributed in the pups. Overall, the safety of ticagrelor during pregnancy has not been established and the use of Teva-Ticagrelor during breastfeeding is not recommended (see 7.1 Special Populations)
- Body Weight: Body weight was determined to have less than a 20% change in the population mean clearance for both ticagrelor and the active metabolite at the 10th or 90th percentile of the body weight distribution compared to the population mean clearance at the median. This small effect on the clearance is not considered clinically relevant. Accordingly, no dose adjustment is necessary for ticagrelor based on weight.
- Ethnic Origin: Patients of Asian descent have a 39% higher bioavailability compared to Caucasian patients. Patients self-identified as Black had an 18% lower bioavailability of ticagrelor compared to Caucasian patients. In clinical pharmacology studies, the exposure (Cmax and AUC) to ticagrelor in Japanese subjects was approximately 40% (20% after adjusting for body weight) higher compared to that in Caucasians. These differences are not considered clinically relevant. The exposure in patients self-identified as Hispanic or Latino was similar to that in Caucasian.
- Smoking: Habitual smoking increased population mean clearance of ticagrelor by approximately 22%. This effect on the clearance is not considered clinically relevant.
- Renal Insufficiency: Exposure to ticagrelor was approximately 20% lower and exposure to the active metabolite was approximately 17% higher in patients with severe renal impairment compared to subjects with normal renal function. The IPA effect of ticagrelor was similar between the two groups, however there was more variability observed in individual response in patients with severe renal impairment. In patients with end stage renal disease on haemodialysis AUC and Cmax of ticagrelor 90 mg administered on a day without dialysis were 38% and 51% higher respectively compared to subjects with normal renal function. A similar increase in exposure was observed when ticagrelor was administered immediately prior to dialysis showing that ticagrelor is not dialysable. Exposure of the active metabolite increased to a lesser extent. The IPA effect of ticagrelor appeared to be unaffected by dialysis in patients with end stage renal disease and was similar to subjects with normal renal function; the clinical impact of these findings is unknown. Appropriate caution should be used in patients requiring renal replacement therapy (see 7.1 Special Populations and Dosing Considerations in Special Populations).
Hepatic Insufficiency: The Cmax and AUC for ticagrelor were 12% and 23% higher in patients with mild hepatic impairment compared to matched healthy subjects,
- No dose adjustment is needed for patients with mild hepatic impairment. No studies have specifically been conducted with ticagrelor in patients with moderate or severe hepatic impairment. Only limited information is available in patients with moderate hepatic impairment. Therefore it is contraindicated for use in patients with moderate or severe hepatic impairment (see 2 CONTRAINDICATIONS and Dosing Considerations in Special Populations).
11 STORAGE, STABILITY AND DISPOSAL
Store at room temperature (15°C - 30°C).
12 SPECIAL HANDLING INSTRUCTIONS
No special requirements.
PART II: SCIENTIFIC INFORMATION
13 PHARMACEUTICAL INFORMATION
Drug Substance
Proper name: Ticagrelor
Chemical name: (1S,2S,3R,5S)-3-[7-{[(1R,2S)-2-(3,4- difluorophenyl)cyclopropyl] amino}-5-(propylthio)-3H-[1,2,3]-triazolo[4,5-d]pyrimidin-3-yl]-5-(2-hydroxyethoxy)cyclopentane-1,2-diol.
OR
(1S, 2S, 3R, 5S)-3-[7-{[(1R, 2S)-2-(3,4-difluorophenyl)cyclopropyl] amino}-5-(propylthio)-3H-[1,2,3]triazolo[4,5-d]pyrimidin-3-yl]-5-(2-hydroxyethoxy)cyclopentane-1,2-diol.
Molecular formula and molecular mass: C23H28F2N6O4S, 522.56 g/mol
Structural formula:
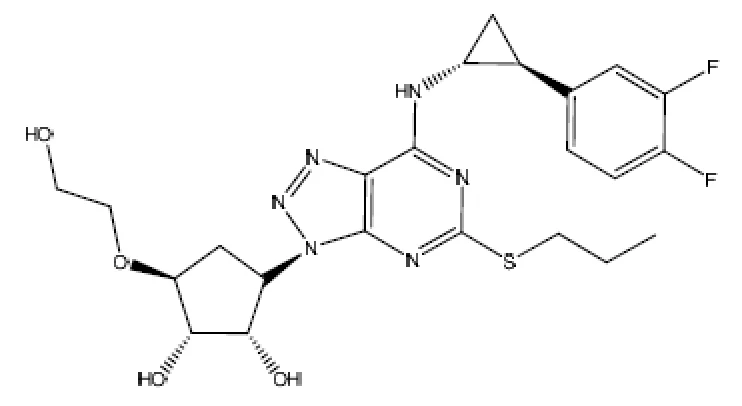
Physicochemical properties: Ticagrelor is white or off white to pale pink powder. Freely soluble in N,N-dimethyl formamide, slightly soluble in methanol and practically insoluble in Water. The specific optical rotation of ticagrelor is between -50° and -60°
14 CLINICAL TRIALS
The safety and efficacy of ticagrelor in preventing atherothrombotic events has been evaluated in three large randomized double-blind trials involving more than 58,000 patients: the PLATO study (ticagrelor 90 mg b.i.d. vs. Clopidogrel 75 mg o.d. both given in combination with acetylsalicylic acid (ASA) and other standard therapy in patients with acute coronary syndrome): the PEGASUS TIMI-54 study (ticagrelor 90 mg b.i.d. and 60 mg b.i.d. both combined with ASA vs. ASA alone in patients with history of spontaneous MI (reported at least 1 year ago) and at risk of an atherothrombotic event) and the THEMIS study (ticagrelor in combination with ASA vs. ASA alone in patients with CAD and type 2 DM).
14.1 Clinical Trials by Indication
Acute Coronary Syndrome
Table 13: Summary of patient demographics for clinical trials in acute coronary syndrome
| Study Name | Study design | Dosage, route of administration and duration | Study subjects (n) | Mean age (Range) | Sex |
|---|---|---|---|---|---|
| PLATO | International, randomized, double-blind, parallel-group study comparing ticagrelor to clopidogrel | Dosage: Ticagrelor (90 mg twice daily) or clopidogrel (75 mg once daily), in combination with ASA; Administration: oral; Duration: up to one year | N=18,624 Ticagrelor n=9,333; Clopidogrel n=9,291 | Mean = 62 years (19-97 years) < 65=57% ≥ 65 years=43% < 75years=85% ≥ 75 years=15% | Male 72% Female 28% |
Study Design
The PLATO study was a Phase III efficacy and safety study of ticagrelor compared with clopidogrel for the prevention of vascular events in patients with ACS (unstable angina [UA], non ST elevation Myocardial Infarction [NSTEMI] or ST elevation Myocardial Infarction [STEMI]).
Patients were randomized to receive ticagrelor (a loading dose of 180 mg followed by a maintenance dose of 90 mg twice daily) or clopidogrel (75 mg once daily, with an initial loading dose of 300 mg if previous thienopyridine therapy had not been given. An additional loading dose of 300 mg was allowed at investigator discretion).
The study was comprised of patients who presented within 24 hours of onset of the most recent episode of chest pain or symptoms. The initiation of treatment in PLATO occurs shortly after symptom onset, prior to the assessment of coronary anatomy by angiography. Patients could have been medically managed, treated with percutaneous coronary intervention (PCI) or coronary artery bypass graft (CABG). Patients were treated for at least 6 months and up to 12 months duration, and patients were followed to study termination, irrespective of whether study drug had been discontinued. The baseline characteristics, medical history, electrocardiographic changes, and drug therapy were similar for both treatment groups.
Study Results
Ticagrelor was superior to clopidogrel in the prevention of thrombotic events (relative risk reduction [RRR] of 16%, absolute risk reduction [ARR] of 1.9%, number needed to treat [NNT] of 54) in the composite efficacy endpoint (primary endpoint) of CV death, MI, and stroke over 12 months in patients with ACS events (UA, NSTEMI and STEMI population) (hazard ratio [HR] 0.84; p=0.0003) (Table 14). The difference in treatments was driven by CV death and MI with no difference on strokes. Ticagrelor demonstrated a statistically significant RRR of 21% (ARR 1.1%) for CV death and a RRR of 16% (ARR 1.1%) for MI, as compared to clopidogrel (Table 14). Treating 91 patients with ticagrelor instead of clopidogrel will prevent 1 CV death.
Ticagrelor reduced the occurrence of the primary composite endpoint compared to clopidogrel in both the UA/NSTEMI and STEMI population.
The Kaplan Meier curve (Figure 3) shows the primary composite endpoint of CV death, MI and Stroke in the UA/NSTEMI and STEMI populations. The treatment effect of ticagrelor was apparent in the first 30 days and the degree of benefit continued to increase throughout the 12 month follow-up.
Figure 3: Time to first occurrence of CV death, MI and stroke (PLATO)
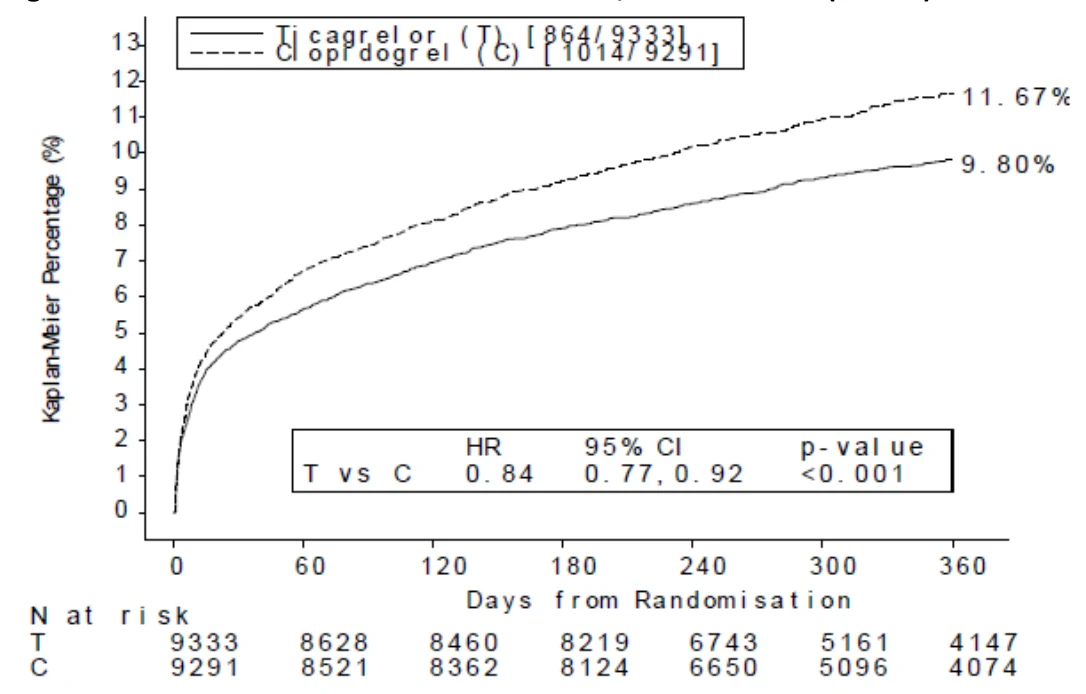
Within the first 30 days of treatment (Figure 4), ticagrelor shows a statistically significant early benefit (ARR 0.6%, RRR 12%), with a constant treatment effect over the entire 12 month period, yielding ARR 1.9% per year with RRR of 16%. Together, these findings demonstrate that the benefit of ticagrelor treatment continues to accrue over 1 to 12 months, and suggests that it is appropriate to treat ACS patients with ticagrelor for at least 12 months.
Figure 4: Primary clinical endpoint by consistency of treatment effect over time at 1-30 days
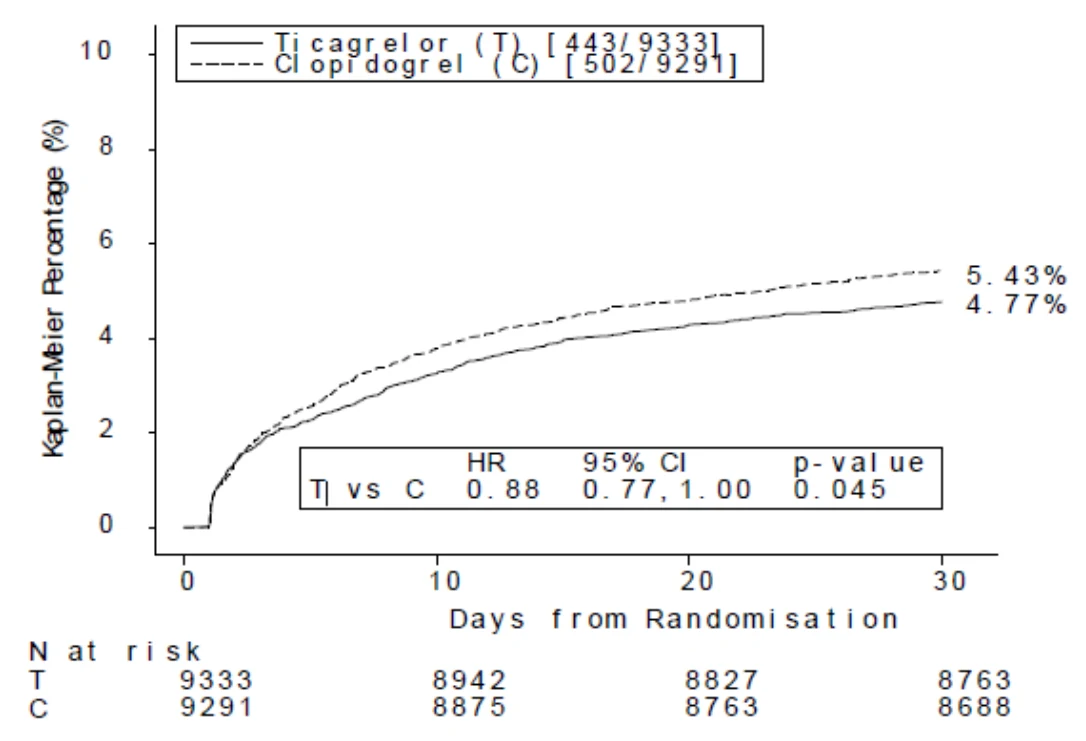
The final secondary endpoint (all-cause mortality) was evaluated. Ticagrelor demonstrated a RRR of 22% for all-cause mortality compared to clopidogrel at a nominal significance level of p=0.0003 and an ARR of 1.4% (Table 14).
| Table 14: Analysis of primary and secondary efficacy endpoints in PLATO (full analysis set) | ||||||||
|---|---|---|---|---|---|---|---|---|
| Patients with Events | RRR (%) | HR (95% CI) | p-value | |||||
Ticagrelor 90 mg twice daily (%) N = 9333 | Clopidogrel 75 mg once daily (%) N = 9291 | |||||||
| Primary Endpoint | ||||||||
| Composite of CV Death/MI (excl. silent MI)/Stroke | 9.3 | 10.9 | 16 | 0.84 (0.77,0.92) | 0.0003 | |||
| Each component of primary efficacy endpoint: | ||||||||
| CV death | 3.8 | 4.8 | 21 | 0.79 (0.69, 0.91) | 0.0013 | |||
| Table 14: Analysis of primary and secondary efficacy endpoints in PLATO (full analysis set) | |||||||||
|---|---|---|---|---|---|---|---|---|---|
| Patients with Events | RRR (%) | HR (95% CI) | p-value | ||||||
Ticagrelor 90 mg twice daily (%) N = 9333 | Clopidogrel 75 mg once daily (%) N = 9291 | ||||||||
| MI (excl. silent MI) | 5.4 | 6.4 | 16 | 0.84 (0.75, 0.95) | 0.0045 | ||||
| Stroke | 1.3 | 1.1 | -17 | 1.17 (0.91, 1.52) | 0.2249 | ||||
| Secondary Endpoints | |||||||||
Composite of CV death/MI (excl. silent MI)/stroke intent to invasively manage | 8.5 | 10.0 | 16 | 0.84 (0.75, 0.94) | 0.0025 | ||||
| Composite of all-cause mortality/MI (excl. silent MI)/stroke | 9.7 | 11.5 | 16 | 0.84 (0.77, 0.92) | 0.0001 | ||||
| Composite of CV Death/Total MI/Stroke/SRI/RI/TIA/Other ATE | 13.8 | 15.7 | 12 | 0.88 (0.81, 0.95) | 0.0006 | ||||
| All-cause mortality | 4.3 | 5.4 | 22 | 0.78 (0.69, 0.89) | 0.0003* | ||||
Note: A single event may be counted in more than 1 row.
ATE Arterial thrombotic events; excl. Excluding; HR Hazard ratio; RI Recurrent cardiac ischaemia; SRI Severe recurrent cardiac ischaemia; TIA Transient ischaemic attack.
* Nominal p-value.
Subgroup Analyses: In PLATO, a large number of subgroup comparisons were conducted for the primary efficacy endpoint to assess the robustness and consistency of the overall benefit. The treatment effect of ticagrelor versus clopidogrel appears consistent across multiple patient subgroups by demographic characteristics including age, gender, weight, diabetes mellitus, planned treatment approach (medically managed or invasive), prior TIA or stroke, medical history, concomitant therapy, and by final index event diagnosis (UA, NSTEMI and STEMI).
A marginally significant treatment interaction was observed with region whereby the HR for the primary endpoint favours ticagrelor in the rest of world but favours clopidogrel in North America, which represented approximately 10% of the overall population studied (interaction p-value=0.045). This apparent treatment-by-region interaction observed in PLATO could plausibly be attributed to chance, at least in part. Additional analyses suggest that the efficacy of ticagrelor relative to clopidogrel is associated with ASA dose during maintenance therapy. The data show greater efficacy of ticagrelor compared to clopidogrel when used in conjunction with low maintenance dose ASA (75-150 mg daily). The relative efficacy of ticagrelor versus clopidogrel when used with high doses of ASA (> 300 mg daily) is less certain. Based on this observed relationship between maintenance ASA dose and relative efficacy of ticagrelor compared to clopidogrel, it is recommended that ticagrelor is used with a daily low maintenance dose of ASA 75-150 mg (see 1 INDICATIONS, 7 WARNINGS AND PRECAUTIONS and 4 DOSAGE AND ADMINISTRATION).
The benefits associated with ticagrelor were also independent of the use of other acute and long-term cardiovascular therapies, including heparin, low molecular weight heparin (LMWH), intravenous GpIIb/IIIa inhibitors, lipid-lowering drugs, beta-blockers, angiotensin-converting enzyme (ACE) inhibitors, angiotensin II receptor antagonists, and proton pump inhibitors (PPIs). The use of oral anticoagulants, and non-study antiplatelet drugs was not allowed in PLATO (see 9 DRUG INTERACTIONS).
Holter Substudy
To study the occurrence of ventricular pauses and other arrhythmic episodes during PLATO, investigators performed Holter monitoring in a subset of nearly 3,000 patients, of whom approximately 2,000 had recordings both in the acute phase of their ACS and after one month. The primary variable of interest was the occurrence of ventricular pauses ≥ 3 seconds. More patients had ventricular pauses with ticagrelor (6.0%) than with clopidogrel (3.5%) in the acute phase; and 2.2% and 1.6% respectively after 1 month. However, there were no adverse clinical consequences associated with this imbalance (including pacemaker insertions) in this population of patients.
PLATO Genetic Substudy
CYP2C19 genotyping of 10,285 patients in PLATO provided associations of genotype groups with the efficacy and safety outcomes. The effects of ticagrelor compared to clopidogrel on major CV events and bleeding were not significantly affected by CYP2C19 genotype. The efficacy and safety results of the substudy were consistent with the main PLATO study.
Patients with History of Myocardial Infarction (≥One Year)
Table 15: Summary of patient demographics for clinical trials in patients with history of myocardial infarction (> one year)
| Study Name | Study design | Dosage, route of administration and duration | Study subjects (n) | Mean age (Range) | Sex |
|---|---|---|---|---|---|
| PEGASUS | Randomized, double-blind, placebo- controlled, parallel-group study | Dosage: 90 mg bid, 60 mg bid, or placebo bid on a background of ASA (75-150 mg od) Administration: Oral Maximum duration: 47 months Event rates calculated at 36 months | N=21,162 90 mg: 7,050 60 mg: 7,045 Placebo: 7,067 | Mean=65 years (50-95 years) < 65 years=46% 65-75 years= 42% >75 years=12% | Male 76% Female 24% |
Study Design
The PEGASUS study assessed the prevention of atherothrombotic events with ticagrelor given at 2 doses (either 90 mg twice daily or 60 mg twice daily) combined with low dose ASA (75-150 mg) compared to ASA therapy alone, in patients with history of spontaneous MI and additional risk factors for atherothrombosis.
Patients were eligible to participate if they were aged 50 years of over, with a history of spontaneous MI (1 to 3 years prior to randomisation), and had at least one of the following risk factors for atherothrombosis: age ≥65 years, diabetes mellitus requiring medication, a second prior MI, evidence of multivessel CAD, and/or chronic non-end-stage renal dysfunction.
Patients were ineligible if there was planned use of ADP receptor antagonist, dipyridamole, cilostazol, or needed chronic anticoagulant therapy; if they had a bleeding disorder or a history of an ischemic stroke or intracranial bleeding, a central nervous system tumour, or an intracranial vascular abnormality; if they had had intracranial or spinal cord surgery within the previous 5 years; if they had had gastrointestinal bleeding within the previous 6 months or major surgery within the previous 30 days.
The PEGASUS study was conducted for a duration up to 47 months with mean (median) duration of exposure to ticagrelor 60 mg of 25.3 months (29.4 months): 5, 481 patients (79%) were exposed for at least 12 months; 4, 505 patients (65%) for at least 24 months; and 1,620 patients (23%) for at least 36 months of extended treatment. Patients were followed to study termination, irrespective of whether study drug had been discontinued.
Study Results
Although the efficacy profile of ticagrelor 90 mg twice daily and 60 mg twice daily were similar, there is evidence that the lower dose has a better tolerability and safety profile in relation to the risk of bleeding and dyspnea. Therefore, ticagrelor 60 mg twice daily co-administered with ASA is the approved dose for the prevention of atherothrombotic events (CV death, MI and stroke) in patients with a history of spontaneous myocardial infarction (MI occurred at least one year ago) and a high risk of developing an atherothrombotic event.
Ticagrelor 60 mg twice daily, in combination with ASA, was superior to ASA alone in the prevention of atherothrombotic events (composite endpoint: CV death, MI and stroke), with a consistent treatment effect over the entire study period, yielding a 16% relative risk reduction [RRR] and 1.27% absolute risk reduction [ARR] (number needed to treat [NNT] of 79) after 36 months of treatment (Table 14). Each of the components contributed to the reduction in the primary composite endpoint (CV death 17% RRR, MI 16% RRR and stroke 25% RRR). Treating 189 patients for up to 36 months with ticagrelor 60 mg twice daily in combination with ASA instead of ASA therapy alone will prevent one CV death.
The benefit of ticagrelor seen on the primary composite endpoint was also reflected across the two secondary endpoints, with a numerical decrease in both CV death and all-cause mortality for ticagrelor 60 mg combined with ASA compared to ASA therapy alone, but this did not reach statistical significance (see Table 16).
Table 16: Analysis of primary and secondary efficacy endpoints in PEGASUS (full analysis set)
| Patients with Events | RRR (%) | HR (95% CI) | p-value | ||||||
|---|---|---|---|---|---|---|---|---|---|
Ticagrelor 60 mg twice daily + ASA N=7045 | ASA alone N=7067 | ||||||||
| Primary Endpoint | |||||||||
| Composite of CV Death/MI/Stroke | 487 (6.9%) | 578 (8.2%) | 16% | 0.84 (0.74, 0.95) | 0.0043 | ||||
| CV death | 174 (2.5%) | 210 (3.0%) | 17% | 0.83 (0.68, 1.01) | 0.0676 | ||||
| MI | 285 (4.0%) | 338 (4.8%) | 16% | 0.84 (0.72, 0.98) | 0.0314 | ||||
| Stroke | 91 (1.3%) | 122 (1.7%) | 25% | 0.75 (0.57, 0.98) | 0.0337 | ||||
| Secondary Endpoint | |||||||||
| CV death | 174 (2.5%) | 210 (3.0%) | 17% | 0.83 (0.68, 1.01) | - | ||||
| All-cause mortality | 289 (4.1%) | 326 (4.6%) | 11% | 0.89 (0.76, 1.04) | - | ||||
Hazard ratio and p-values are calculated separately for ticagrelor versus ASA alone from Cox proportional hazards model with treatment group as the only explanatory variable.
Note: the number of first events for the components CV Death, MI and Stroke are the actual number of first events for each component and do not add up to the number of events in the composite endpoint.
CI = Confidence interval; CV = Cardiovascular; HR = Hazard ratio; MI = Myocardial infarction; N = Number of patients.
The RRR for the composite endpoint from 1 to 360 days (17% RRR) and from 361 days and onwards (16% RRR) was similar. The Kaplan-Meier plot (Figure 5) shows the analysis of the primary clinical composite endpoint of CV death, MI and stroke.
Treatment with ticagrelor should be continued in patients with a history of spontaneous MI for as long as the patient remains at high risk of an atherothrombotic event for a duration up to three years. Efficacy and safety data are insufficient to establish whether the benefits of ticagrelor still outweigh the risks after three years of extended treatment (see 4 DOSAGE AND ADMINISTRATION).
Figure 5: Primary clinical composite endpoint of CV death, MI and stroke in PEGASUS (full analysis set)
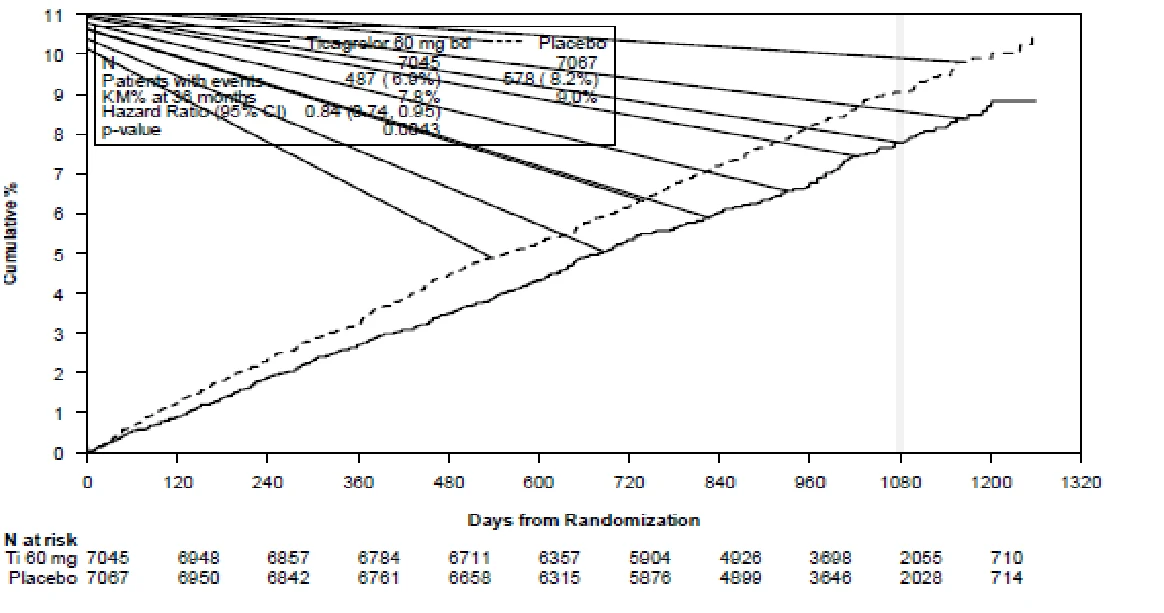
Analysis of patient subgroups
The treatment effect of ticagrelor 60 mg twice daily versus ASA across major subgroups is presented in Figure 6. There was no evidence of benefit (no reduction in the primary composite endpoint of CV death, MI and stroke), but an increase in major bleedings when ticagrelor 60 mg twice daily was introduced in clinically stable patients more than 2 years after the qualifying MI, or more than one year after stopping previous ADP receptor antagonist treatment. This also resulted in numerical increases in CV death and all-cause mortality (see 4 DOSAGE AND ADMINISTRATION).
Figure 6: Hazard ratios and rates of the primary clinical composite endpoint of CV death, MI and stroke by patient subgroup in PEGASUS (full analysis set)
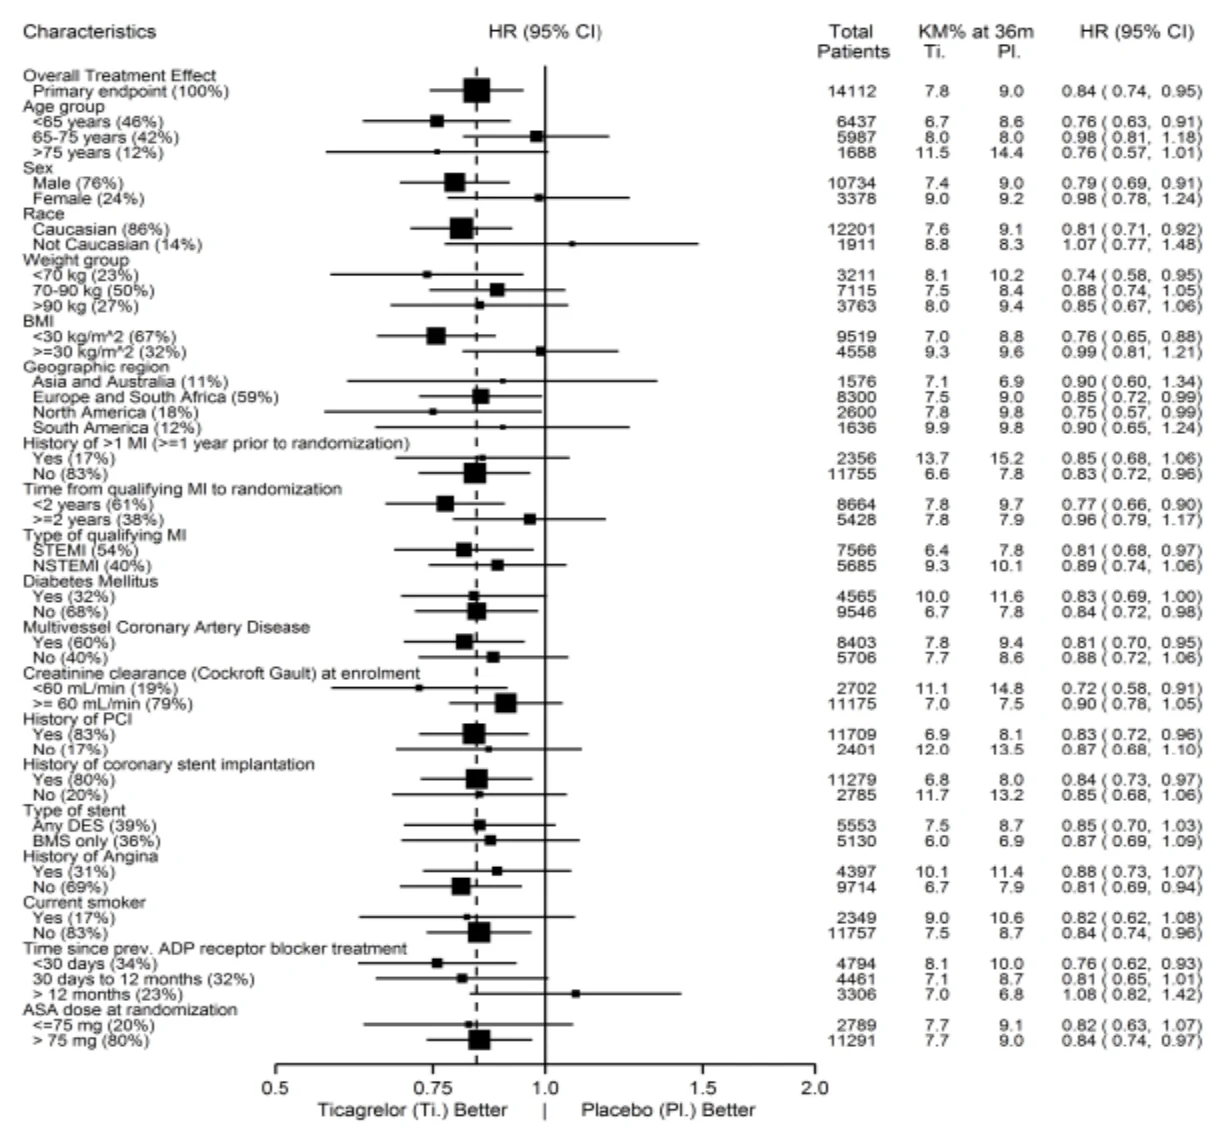
Patients with Coronary Artery Disease and Type 2 Diabetes Mellitus with a History of Percutaneous Coronary Intervention
Table 17: Summary of patient demographics for clinical trials in patients with coronary artery disease and type 2 diabetes mellitus with a history of percutaneous coronary intervention
| Study Name | Study design | Dosage, route of administration and duration | Study subjects (n) | Mean age (Range) | Sex |
|---|
| THEMIS | Randomized, double-blind, placebo-controlled, parallel-group study | Dosage: Ticagrelor or placebo twice daily on a background of ASA (75-150 mg od) Administration: Oral Maximum Duration: 57 months Event rates calculated at 36 months | N=19,220 Ticagrelor: n=9619 Placebo: n=9601 Patients with history of PCI: N=11,154 Ticagrelor: n=5558 Placebo: n=5596 | Mean = 66 years (46 to 95 years) < 65 years=41% 65-75 years=46% >75 years=13% | Male 69% Female 31% |
|---|
Study Design
The THEMIS study was a 19,220 patient, event-driven, randomized, double-blind, placebo-controlled, parallel group, international multi-centre study to assess the prevention of atherothrombotic events with ticagrelor combined with low dose ASA (75-150 mg) compared to ASA therapy alone in patients with CAD and type 2 DM. The median ticagrelor treatment duration was 33.2 months.
Patients were eligible to participate if they were aged 50 years or over, had CAD defined as history of PCI (58% of study population) or CABG (29%) or no history of coronary revascularisation, but angiographic evidence of ≥ 50% lumen stenosis of at least 1 coronary artery (20%) and type 2 DM treated with glucose-lowering medication for at least 6 months prior to study start.
Patients were ineligible to participate if they had a history of MI or stroke; if there was planned use of ADP receptor antagonists, ASA treatment >150 mg od, dipyridamole, or cilostazol; if there was planned coronary, cerebrovascular, or peripheral arterial revascularization or anticipated use of CYP3A4 substrates with narrow therapeutic indices or strong CYP3A4 inhibitors; if they were at known increased risk for bleeding (e.g., need for chronic oral anticoagulants, known bleeding diathesis, coagulation disorder, recent major surgery, history of previous intracerebral bleed or GI bleeding within the past 6 months etc.) or bradycardic events unless treated with a pacemaker; if they had uncontrolled hypertension or renal failure requiring dialysis, or if they had any contraindications to receive ticagrelor treatment.
THEMIS study was conducted for a duration up to 57 months with mean (median) duration of exposure to ticagrelor of 29.2 months (33.2 months). With respect to duration of exposure to the study drug, 7322 (76.6%) patients were exposed to ticagrelor for 12 months, 6421 (67.2%) for 24 months and 4107 (43%) for 36 months. At 48 months, 1175 (12.3%) patients were exposed to ticagrelor. Patients were followed to study termination, irrespective of whether study drug had been discontinued.
Study Results In the total THEMIS study population, ticagrelor twice daily in combination with ASA, compared to ASA alone, resulted in the prevention of atherothrombotic events (composite endpoint: CV death, MI and stroke), with a hazard ratio (HR) of 0.90 (95% CI: 0.81, 0.99, p=0.0378), corresponding to a relative risk reduction (RRR) of 10% and an absolute risk reduction (ARR) of 0.73% (number needed to treat [NNT] of 138 after 36 months of treatment). The effect was driven by the individual components MI (HR 0.84, 95% CI: 0.71, 0.98) and stroke (HR 0.82, 95% CI: 0.67, 0.99), with no difference in CV deaths (HR 1.02, 95% CI: 0.88, 1.18). Of the secondary endpoints not assessed as part of the primary composite endpoint, ticagrelor reduced the number of ischemic stroke events (HR 0.80, 95% CI: 0.64, 0.99) with no difference in all-cause death (HR 0.98, 95% CI 0.87, 1.10). The benefit-risk profile of ticagrelor in the total THEMIS study population was not considered favourable to support use of ticagrelor and therefore, an indication was not granted for the total study population (see 1 INDICATIONS and 7 WARNINGS AND PRECAUTIONS).
In THEMIS patients with a history of PCI, which was a pre-specified subgroup corresponding to 58% of the total study population, treatment with ticagrelor in combination with ASA, compared to ASA alone, resulted in the prevention of atherothrombotic events (composite endpoint: CV death, MI and stroke) (see Table 18). Ticagrelor treatment yielded a 15% RRR, a 1.19% ARR (number needed to treat [NNT] of 84 after 36 months of treatment) and a more favourable benefit-risk profile than the total THEMIS study population. Again, the treatment benefit was driven by the MI and stroke components of the composite endpoint.
The baseline characteristics in the subgroup of patients with a history of PCI were comparable in both treatment arms.
Table 18: Analysis of primary and secondary efficacy endpoints in the subgroup of THEMIS patients with a history of PCI (full analysis set)
| Patients with Events | RRR (%) | HR (95% CI) | p-valuea | |||||||
|---|---|---|---|---|---|---|---|---|---|---|
Ticagrelor twice daily + ASA N=5558 | ASA alone N = 5596 | |||||||||
| Primary Endpoint | ||||||||||
| Composite of CV Death/MI/Stroke | 404 (7.3%) | 480 (8.6%) | 15% | 0.85 (0.74, 0.97) | 0.0133 | |||||
| CV death | 174 (3.1%) | 183 (3.3%) | 4% | 0.96 (0.78, 1.18) | 0.6803 | |||||
| MI | 171 (3.1%) | 216 (3.9%) | 20% | 0.80 (0.65, 0.97) | 0.0266 | |||||
| Stroke | 96 (1.7%) | 131 (2.3%) | 26% | 0.74 (0.57, 0.96) | 0.0243 | |||||
| Secondary Endpoint | ||||||||||
| CV death | 174 (3.1%) | 183 (3.3%) | 4% | 0.96 (0.78, 1.18) | - | |||||
| MI | 171 (3.1%) | 216 (3.9%) | 20% | 0.80 (0.65, 0.97) | - |
|---|---|---|---|---|---|
| Ischaemic Stroke | 88 (1.6%) | 113 (2.0%) | 21% | 0.79 (0.59, 1.04) | - |
| All-cause deathb | 282 (5.1%) | 323 (5.8%) | 12% | 0.88 (0.75, 1.03) | - |
Hazard ratio and p-values are calculated for ticagrelor twice daily + ASA vs ASA alone from Cox proportional hazards model with treatment as the only explanatory variable. The number of first events for the components CV death, MI and stroke are the actual number of first events for each component and do not add up to the number of events in the composite endpoint
CI = Confidence interval; CV = Cardiovascular; HR = Hazard ratio; MI = Myocardial infarction; N = Number of patients in treatment group; RRR = Relative risk reduction.
1p-values are nominal.
b Includes deaths based on publicly available vital status data in patients who have withdrawn consent.
Treatment with Teva-Ticagrelor should be continued in patients with CAD, type 2 DM and history of PCI for as long as the patient remains at high risk of an atherothrombotic event and low risk of bleeding, for a duration up to three years. Efficacy and safety data are insufficient to establish whether the benefits of ticagrelor still outweigh the risks after three years of extended treatment (see 4 DOSAGE AND ADMINISTRATION).
Figure 7: Kaplan-Meier plot and analysis of primary clinical composite endpoint of CV death, MI and stroke in THEMIS patients with a history of PCI (full analysis set)
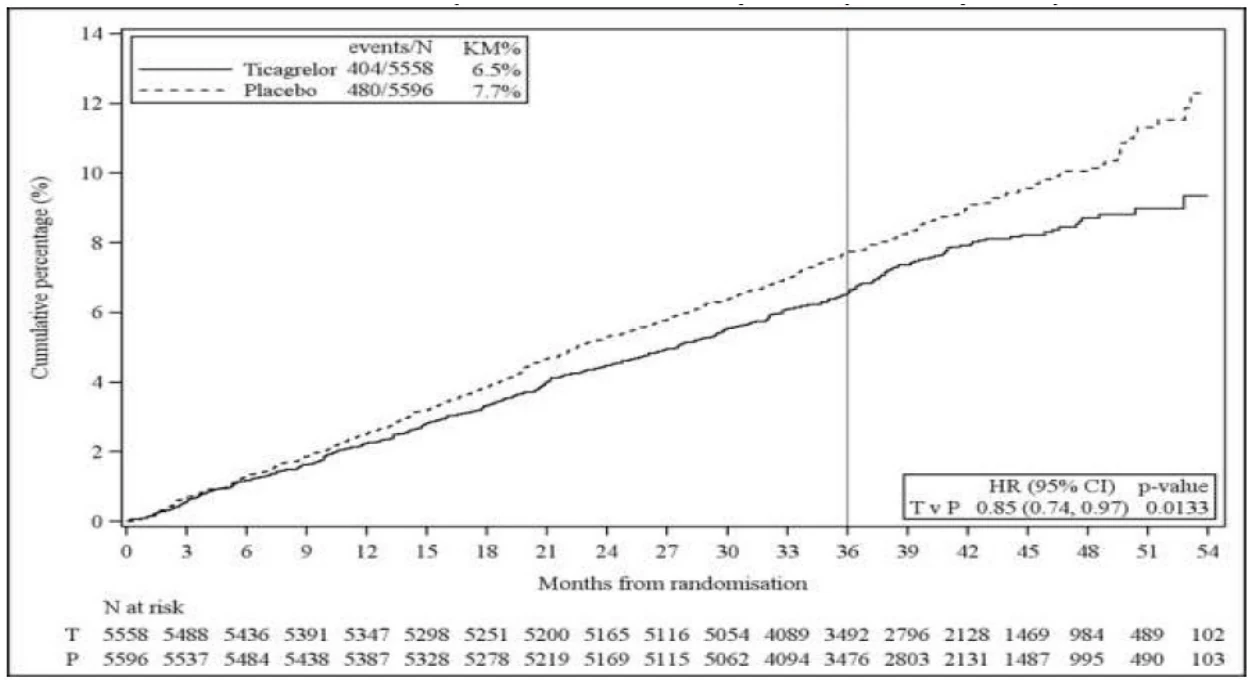
The treatment effect of ticagrelor across patient subgroups, based on patient characteristics including weight, gender, medical history, and geographic region, in THEMIS patients with a history of PCI is shown in Figure 8.
Figure 8: Hazard ratios and rates of the primary clinical composite end point of CV death, MI and stroke by patient subgroup in THEMIS PCI patients (full analysis set)
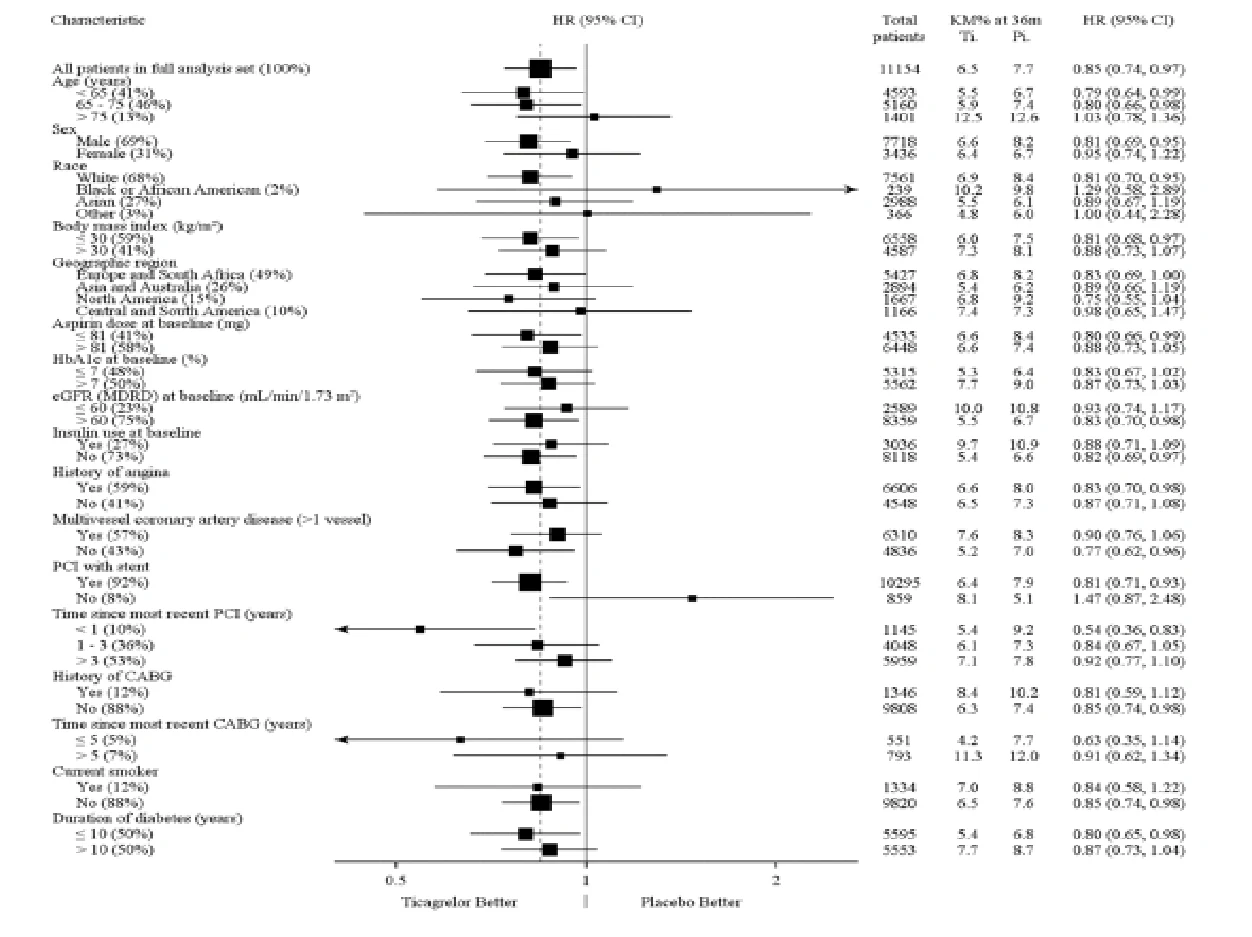
14.2 Comparative Bioavailability Studies
A double blinded, randomized, single dose, two-way crossover study of Teva-Ticagrelor (ticagrelor) Tablets, 90 mg (Teva Canada Limited) and BRILINTA® (ticagrelor) Tablets, 90 mg (AstraZeneca Canada Inc.), administered as a single 1 x 90 mg dose, was conducted in healthy, adult, female, Asian Indian subjects under fasting conditions.
The results of the measured data from the 26 subjects who were included in the statistical population are summarized in the table below.
Ticagrelor (1 x 90 mg) Geometric Mean Arithmetic Mean (CV %) | ||||
|---|---|---|---|---|
| Parameter | Test1 | Reference2 | % Ratio of Geometric Means | 90% Confidence Interval |
AUCT (ng ·h/ml) | 6738.2 7170.9 (35.9) | 6441.9 6882.2 (35.3) | 104.6 | 99.5 - 110.0 |
AUCI (ng ·h/ml) | 6980.4 7418.7 (35.6) | 6688.6 7117.2 (34.4) | 104.4 | 99.5 - 109.5 |
Cmax (ng /mL) | 983.7 1028.9 (30.1) | 984.1 1025.3 (26.5) | 100.0 | 91.1 - 109.7 |
Tmax3 (h) | 2.7 (1.4 - 5.0) | 2.0 (1.3 - 4.0) | ||
T½4 (h) | 9.2 (24.6) | 8.9 (29.2) | ||
1 TEVA-TICAGRELOR (ticagrelor) tablets, 90 mg (Teva Canada Limited)
2 PrBRILINTA® (ticagrelor) tablets, 90 mg (AstraZeneca Canada Inc.)
3 Expressed as the median (range) only
4 Expressed as the arithmetic mean (CV %) only
15 MICROBIOLOGY
No microbiological information is required for this drug product.
16 NON-CLINICAL TOXICOLOGY
General Toxicology
Acute toxicity: The acute toxicity of ticagrelor is considered low. The results of single dose studies in CD-1 mice and Sprague-Dawley rats showed that ticagrelor was well tolerated when given orally by gavage following doses up to 2000 mg/kg (the highest dose tested). This dose represents approximately 550 times the recommended human daily dose on a mg/kg basis.
Chronic toxicity: Repeat-dose studies were conducted in mice, rats and marmosets. Consistent observations across species in repeat dose studies were seen primarily in the gastrointestinal tract, but were inconsistent with respect to the location, severity, and type of the observations. Indications of subclinical bleeding were also observed across species.
Increased liver weight at high doses occurred in rodents. In rats, this was accompanied by centrilobular hypertrophy and induction of cytochrome P450 liver enzymes, and was reversible upon withdrawal of treatment.
Adrenal weights increased at higher doses in the repeat dose studies in rodents, and were reversible upon withdrawal of treatment.
The metabolic pathways for ticagrelor were found to be qualitatively similar across species and no human specific metabolites were detected.
Carcinogenicity: No ticagrelor-related tumours were observed in a 2-year mouse study at oral doses up to 250 mg/kg/day (>18-fold the maximum human therapeutic exposure). There was no increase in tumours in male rats at oral doses up to 120 mg/kg/day (>15-fold the maximum human therapeutic exposure). There was an increase in uterine adenocarcinomas and hepatocellular adenomas plus adenocarcinomas and a decrease in pituitary adenomas and mammary fibroadenomas in female rats only exposed to high doses (>25-fold the maximum human therapeutic exposures). No change in individual tumour incidence was observed at 60 mg/kg/day (8-fold difference to the maximum human therapeutic exposure). When ovarian sex cord/stromal tumors were combined, there was a small, but statistically significant (Peto analysis) increase for the low- and high-dose female rats, but not for the mid-dose females. A treatment-related effect on combined ovarian sex cord/stromal tumors is uncertain due to the low incidence values, but cannot definitively be ruled out. Plasma exposures for the low dose females were 1.5 times greater than therapeutic exposures in humans. The uterine tumours seen only in rats were found to be the result of a non-genotoxic endocrine effect of hormonal imbalance triggered by inhibition of prolactin secretion in rats given high doses of ticagrelor. This mechanism of uterine tumour formation in rats is not relevant to humans. The benign liver tumours are considered likely related to the pleiotropic response that included increased liver weight, hepatocellular hypertrophy, and microsomal enzyme induction.
Genotoxicity: Ticagrelor and the active metabolite AR-C124910XX do not demonstrate any genotoxic potential in bacterial, in vitro mouse lymphoma L5178Y TK+/- 3.7.2C cell, and in vivo rat bone marrow micronucleus assays. The active metabolite AR-C124910XX was not genotoxic in the same in vitro assays.
Reproductive and Developmental Toxicology: Ticagrelor was found to have no effect on fertility of female rats at oral doses up to 200 mg/kg/day (approximately 20 times the maximum human therapeutic exposure) and had no effect on fertility of male rats at doses up to 180 mg/kg/day (15.7 times the maximum human therapeutic exposure).
Ticagrelor given during the period of organogenesis had no effect on fetal development at oral doses up to 100 mg/kg/day in rats (5.1 times the maximum human therapeutic exposure) and up to 42 mg/kg/day in rabbits (equivalent to the maximum human therapeutic exposure). Fetal effects that were considered to be developmental variants or delays were seen in fetuses from female rats given 300 mg/kg (decreased body weight, 27 pre-pelvic vertebral arches, extra 14th ribs, and incomplete ossification of various skeletal structures), that may have resulted from maternal toxicity, and fetal developmental delays were also seen in rabbits given 63 mg/kg (increased incidences of clear gall bladder contents, incompletely ossified hyoid and pubis, one or more incomplete ossification of various skeletal structures), at which there was no overt maternal toxicity.
Ticagrelor had no effects on parturition or postnatal development in rats at doses up to 60 mg/kg/day (4.6 times the maximum human therapeutic exposure), but did cause maternal (reduced body weight gain and food consumption) and developmental toxicity in pups (reduced post-natal viability, lower birth weight, and delayed growth and physical development) at 180 mg/kg.
17 SUPPORTING PRODUCT MONOGRAPHS
BRILINTA® (ticagrelor tablets, 60 mg and 90 mg), Submission Control Number 286653, Product Monograph, AstraZeneca Canada Inc., SEP 20, 2024.