


Product Monograph - Treprostinil Injection (Marcan Pharmaceuticals)
Recent Major Label Changes
| 7 Warnings and Precautions | 2026-08 |
|---|
Table of Contents
Sections or subsections that are not applicable at the time of authorization are not listed.
Recent Major Label Changes ...................................................................................................................... 2
Table of Contents ....................................................................................................................................... 2
Part 1: Healthcare Professional Information ............................................................................................... 4
- 1.
Indications .......................................................................................................................................... 4
1.1 Pediatrics .................................................................................................................................. 4
1.2 Geriatrics ................................................................................................................................... 4
- 2. Contraindications................................................................................................................................ 4
- 4.
Dosage and Administration ................................................................................................................. 4
4.1 Dosing Considerations .............................................................................................................. 4
4.2 Recommended Dose and Dosage Adjustment ......................................................................... 4
4.3 Reconstitution ........................................................................................................................... 5
4.4 Administration .......................................................................................................................... 5
4.5 Missed Dose .............................................................................................................................. 9
- 5. Overdose ............................................................................................................................................ 9
- 6. Dosage Forms, Strengths, Composition, and Packaging ..................................................................... 10
- 7.
Warnings and Precautions ................................................................................................................ 11
General ................................................................................................................................................ 11
Carcinogenesis and Genotoxicity .............................................................................................................. 11
Hepatic/Biliary/Pancreatic ........................................................................................................................ 11
Pulmonary Veno-Occlusive Disease .......................................................................................................... 11
Renal ................................................................................................................................................ 12
Risk of Catheter-Related Blood Stream Infections ................................................................................... 12
7.1 Special Populations ................................................................................................................. 12
7.1.1 Pregnancy ............................................................................................................................... 12
7.1.2 Breastfeeding .......................................................................................................................... 12
7.1.3 Pediatrics ................................................................................................................................ 12
7.1.4 Geriatrics ................................................................................................................................. 12
- 8.
Adverse Reactions ............................................................................................................................ 12
8.1 Adverse Reaction Overview .................................................................................................... 12
8.2 Clinical Trial Adverse Reactions .............................................................................................. 13
8.5. Post-Market Adverse Reactions ......................................................................................................... 17
- 9.
Drug Interactions .............................................................................................................................. 17
9.2 Drug Interactions Overview .................................................................................................... 17
9.3 Drug-Behavior Interactions ..................................................................................................... 17
9.4 Drug-Drug Interactions ........................................................................................................... 17
- 10.
Clinical Pharmacology ....................................................................................................................... 18
10.1 Mechanism of Action .............................................................................................................. 18
10.2 Pharmacodynamics ................................................................................................................. 18
10.3 Pharmacokinetics .................................................................................................................... 19
- 11. Storage, Stability, and Disposal ......................................................................................................... 21
- 12. Special Handling Instructions ............................................................................................................ 21
Part 2: Scientific Information .................................................................................................................... 22
- 13. Pharmaceutical Information ............................................................................................................. 22
- 14.
Clinical Trials .................................................................................................................................... 23
14.1 Clinical Trials by Indication ...................................................................................................... 23
Treatment of Pulmonary Arterial Hypertension in NYHA Class II and IV Patients Who Do Not Respond Adequately to Conventional Therapy ..................................................................................... 23
14.2 Comparative Bioavailability Studies ........................................................................................ 24
- 16. Non-Clinical Toxicology ....................................................................................................................... 25
- 17. Supporting Product Monographs ...................................................................................................... 29
Patient Medication Information ............................................................................................................... 30
Part 1: Healthcare Professional Information
1. Indications
Treprostinil Injection (treprostinil) is indicated for the long-term, subcutaneous or intravenous treatment of pulmonary arterial hypertension (PAH) in NYHA Class III and IV patients who did not respond adequately to conventional therapy.
Treprostinil Injection should be used only by healthcare professionals experienced in the diagnosis and treatment of PAH. Treprostinil Injection is a potent pulmonary and systemic vasodilator. Initiation of Treprostinil Injection must be performed in a setting with adequate personnel and equipment for physiological monitoring and emergency care. Treprostinil Injection is infused continuously through a subcutaneous or surgically placed indwelling central venous catheter.
1.1 Pediatrics
Pediatrics (<16 years of age): Safety and effectiveness in pediatric patients have not been established; therefore, Health Canada has not authorized an indication for pediatric use (see 7.1.3 Pediatrics and 10.3 Pharmacokinetics).
1.2 Geriatrics
Geriatrics (>65 years of age): Safety and effectiveness in geriatric patients have not been established; therefore, Health Canada has not authorized an indication for geriatric use (see 7.1.4 Geriatrics).
2. Contraindications
Treprostinil Injection is contraindicated in patients with known hypersensitivity to the drug, any of its excipients, or to structurally related compounds. For a complete listing, see 6 Dosage Forms, Strengths, Composition, and Packaging.
4. Dosage and Administration
4.1 Dosing Considerations
Treprostinil Injection is indicated for subcutaneous or intravenous use only. Treprostinil Injection should be prescribed only by healthcare professionals experienced in the diagnosis and treatment of PAH.
Dosage adjustments in clinical trials were based on the patient’s signs and symptoms of PAH and side effects of treprostinil. Dosage of Treprostinil Injection should be adjusted at the first sign of recurrence or worsening of symptoms attributable to PAH or the occurrence of intolerable adverse events associated with Treprostinil Injection.
Therapy with Treprostinil Injection may be used for prolonged periods, and the patient’s ability to administer Treprostinil Injection and care for an infusion system should be carefully considered. In order to reduce the risk of infection, aseptic technique must be used in the preparation and administration of Treprostinil Injection.
4.2 Recommended Dose and Dosage Adjustment
Treprostinil Injection can be administered without further dilution for subcutaneous administration, or diluted for intravenous infusion with 0.9% Sodium Chloride Injection or Sterile Water for Injection at concentrations as low as 0.004 mg/mL prior to administration.
Initial Dose: Treprostinil Injection is administered by continuous subcutaneous or continuous intravenous infusion. Treprostinil Injection is preferably infused subcutaneously, but can be administered by a central intravenous line if the subcutaneous route is not tolerated, because of severe site pain or reaction. The infusion rate is initiated at 1.25 ng/kg/min. If this initial dose cannot be tolerated, because of systemic effects, reduce the infusion rate to 0.625 ng/kg/min.
The goal of chronic dosage adjustments is to establish a dose at which PAH symptoms are improved, while minimizing excessive pharmacologic effects of Treprostinil Injection (headache, nausea, emesis, restlessness, anxiety and infusion site pain or reaction).
The infusion rate should be increased in increments of 1.25 ng/kg/min per week for the first four weeks of treatment and then 2.5 ng/kg/min per week for the remaining duration of infusion depending on clinical response. Dosage adjustment may be undertaken more often if tolerated and adjusted based on PAH signs and symptoms and Treprostinil Injection side effects. Dose-related symptoms may necessitate a decrease in infusion rate; however, the event may resolve without dosage adjustment. Should an adverse event worsen and/or become intolerable, the infusion rate should be reduced, or infusion should be discontinued. Abrupt cessation of infusion should be avoided (see 7 Warnings and Precautions). Restarting a Treprostinil Injection infusion within a few hours after interruption can be done using the same dose rate. Interruptions for longer periods may require the dose of Treprostinil Injection to be re-titrated.
Effects of Other Drugs on Treprostinil
Co-administration of a cytochrome P450 (CYP) 2C8 enzyme inhibitor (e.g., gemfibrozil) increases exposure (both Cmax and AUC) to treprostinil. Treprostinil Injection dose reduction should be considered.
Co-administration of a CYP2C8 enzyme inducer (e.g., rifampin) decreases exposure to treprostinil. Treprostinil Injection dose increases should be considered (see 9.4 Drug-Drug Interactions).
Dosage in Patients with Hepatic Impairment: Patients with mild to moderate hepatic insufficiency will require dosing modifications. In patients with mild to moderate hepatic insufficiency, decrease the initial dose of Treprostinil Injection to 0.625 ng/kg/min ideal body weight. The dose should be increased more conservatively in patients with hepatic dysfunction, and these patients should be closely monitored for signs and symptoms or emergence of adverse events due to excess Treprostinil Injection. Treprostinil has not been studied in patients with severe hepatic insufficiency (see 7 Warnings and Precautions).
4.3 Reconstitution
Parenteral Products:
- Treprostinil Injection does not require reconstitution.
4.4 Administration
Treprostinil Injection should be inspected visually for clarity, particulate matter, precipitate, discoloration and leakage prior to administration whenever solution and container permit. Solutions showing haziness, particulate matter, discoloration, or leakage should not be used. Discard unused portion.
Treprostinil Injection is administered using a suitable ambulatory infusion pump that should:
- (1) be small and lightweight,
- (2) be able to adjust infusion rates in approximately 0.002 mL/hr,
- (3) have occlusion/no delivery, low battery, programming error and motor malfunction alarms,
- (4) have delivery accuracy of ±6% or better, and
- (5) be positive pressure driven.
The reservoir should be made of polyvinyl chloride, polypropylene, or glass.
Subcutaneous Infusion
Treprostinil Injection is administered subcutaneously by continuous infusion without further dilution, via a self-inserted subcutaneous catheter, using an infusion pump designed for subcutaneous drug delivery. To avoid potential interruptions in drug delivery, the patient must have immediate access to a backup infusion pump and subcutaneous infusion sets.
For subcutaneous infusion, Treprostinil Injection is delivered without further dilution at a calculated Subcutaneous Infusion Rate (mL/hr) based on a patient’s Dose (ng/kg/min), Weight (kg), and the Vial Strength (mg/mL) of Treprostinil Injection being used. During use, a single reservoir (syringe) of undiluted Treprostinil Injection can be administered up to 72 hours at 37°C.
The Subcutaneous Infusion Rate is calculated using the following formula:
Subcutaneous Infusion Rate (mL/hr)
Dose (ng/kg/min) x Weight (kg) x 0.00006*
=
Treprostinil Injection Vial Strength (mg/mL)
*Conversion factor of 0.00006 = 60 min/hour x 0.000001 mg/ng Example calculations for Subcutaneous Infusion are as follows:
Example 1:
For a 60 kg person at the recommended initial dose of 1.25 ng/kg/min using the 1 mg/mL Treprostinil Injection Vial Strength, the infusion rate would be calculated as follows:
Subcutaneous Infusion Rate (mL/hr)
1.25 ng/kg/min x 60 kg x 0.00006
=
1 mg/mL
= 0.005 mL/hr
Example 2:
For a 65 kg person at a dose of 40 ng/kg/min using the 5 mg/mL Treprostinil Injection Vial Strength, the infusion rate would be calculated as follows:
Subcutaneous Infusion Rate (mL/hr)
40 ng/kg/min x 65 kg x 0.00006
=
5 mg/mL
= 0.031 mL/hr
Intravenous Infusion
Treprostinil Injection must be diluted with Sterile Water for Injection, or 0.9% Sodium Chloride Injection prior to administration. Diluted Treprostinil Injection is administered intravenously by continuous infusion, via a surgically placed indwelling central venous catheter, using an infusion pump designed for intravenous drug delivery. If clinically necessary, a temporary peripheral intravenous cannula, preferably placed in a large vein, may be used for short term administration of Treprostinil Injection. Use of a peripheral intravenous infusion for more than a few hours may be associated with an increased risk of thrombophlebitis. To avoid potential interruptions in drug delivery, the patient must have immediate access to a backup infusion pump and infusion sets. The infusion set should also contain 0.22 or 0.2 µm pore size in-line filter and an anti-siphon valve.
Diluted Treprostinil Injection has been shown to be stable at ambient temperature for up to 48 hours using 0.9% Sodium Chloride Injection or Sterile Water for Injection as the diluent at concentrations as low as 0.004 mg/mL.
When using an appropriate infusion pump and reservoir, a predetermined intravenous infusion rate should first be selected to allow for a desired infusion period length of up to 48 hours between system changes. Typical intravenous infusion system reservoirs have volumes of 50 or 100 mL. With this selected Intravenous Infusion Rate (mL/hr) and the patient’s Dose (ng/kg/min) and Weight (kg), the
Diluted Intravenous Treprostinil Injection Concentration (mg/mL) can be calculated using the following formula:
Step 1
Diluted
Intravenous Treprostinil
Concentration
(mg/mL)
= Dose (ng/kg/min) x Weight (kg) x 0.00006
Intravenous Infusion Rate (mL/hr)
The Volume of Treprostinil Injection needed to make the required Diluted Intravenous Treprostinil Injection Concentration for the given reservoir size can then be calculated using the following formula:
Step 2
Volume of Treprostinil Injection
(mL)
Diluted Intravenous Treprostinil Injection
Concentration (mg/mL) x
= Treprostinil Injection Vial Strength (mg/mL)
Total Volume of Diluted Treprostinil Injection Solution in Reservoir
(mL)
The calculated Volume of Treprostinil Injection is then added to the reservoir along with the sufficient volume of diluent to achieve the desired total volume in the reservoir.
Example calculations for Intravenous Infusion are as follows:
Example 3:
For a 60 kg person at a dose of 5 ng/kg/min, with a predetermined intravenous infusion rate of 1 mL/hr and a reservoir of 50 mL, the Diluted Intravenous Treprostinil Injection Solution Concentration would be calculated as follows:
Step 1
Diluted
Intravenous Treprostinil Injection
Concentration
(mg/mL)
5 ng/kg/min x 60 kg x 0.00006
= 1 mL/hr
= 0.018 mg/mL
(18,000 ng/mL)
The Volume of Treprostinil Injection (using 1 mg/mL Vial Strength) needed for a total Diluted Treprostinil Injection Concentration of 0.018 mg/mL and a total volume of 50 mL would be calculated as follows:
Step 2
Volume of
0.018 mg/mL
Treprostinil Injection =
(mL)
1 mg/mL
x 50 mL = 0.9 mL
The Diluted Intravenous Treprostinil Injection Concentration for the person in Example 3 would thus be prepared by adding 0.9 mL of 1 mg/mL Treprostinil Injection to a suitable reservoir along with a sufficient volume of diluent to achieve a total volume of 50 mL in the reservoir. The pump flow rate for this example would be set at 1 mL/hr.
Example 4:
For a 75 kg person at a dose of 30 ng/kg/min, with a predetermined intravenous infusion rate of
2 mL/hr, and a reservoir of 100 mL, the Diluted Intravenous Treprostinil Injection Solution Concentration would be calculated as follows:
Step 1
Diluted
Intravenous
30 ng/kg/min x 75 kg x 0.00006 = 0.0675 mg/mL
TREPROSTINIL =
Concentration
(mg/mL)
2 mL/hr
(67,500 ng/mL)
The Volume of Treprostinil Injection (using 2.5 mg/mL Vial Strength) needed for a total Diluted Treprostinil Injection Concentration of 0.0675 mg/mL and a total volume of 100 mL would be calculated as follows:
Step 2
Volume of TREPROSTINIL Injection (mL)
= 0.0675 mg/mL x 100 mL = 2.7 mL
2.5 mg/mL
The Diluted Intravenous Treprostinil Injection Concentration for the person in Example 4 would thus be prepared by adding 2.7 mL of 2.5 mg/mL Treprostinil Injection to a suitable reservoir along with a sufficient volume of diluent to achieve a total volume of 100 mL in the reservoir. The pump flow rate for this example would be set at 2 mL/hr.
4.5 Missed Dose
As with any potent vasodilator, abrupt withdrawal or sudden large reductions in dosage of Treprostinil Injection may result in worsening of PAH symptoms. Abrupt withdrawal of Treprostinil Injection should be avoided if at all possible. If a scheduled dose is missed or interrupted, therapy should be resumed as soon as possible. Restarting a Treprostinil Injection infusion within a few hours after an interruption can be done using the same dose rate. Interruptions for longer periods may require the dose of Treprostinil Injection to be re-titrated.
5. Overdose
Signs and symptoms of overdose with treprostinil during clinical trials are extensions of its dose-limiting pharmacologic effects and include flushing, headache, hypotension, nausea, vomiting, and diarrhea. Most events were self-limiting and resolved with reduction or withholding of treprostinil.
In controlled clinical trials, seven patients received some level of overdose and in chronic, open-label follow-on treatment, seven additional patients received an overdose; these occurrences resulted from accidental bolus administration of treprostinil, errors in pump programmed rate of administration, and prescription of incorrect dose. The amount of excess treprostinil actually administered varied in each patient. Three placebo patients in controlled clinical trials were inadvertently administered treprostinil with doses initiated at 8.5, 10 and 15 ng/kg/min, respectively. Six patients received excess treprostinil due to incorrect pump settings (excess doses ranged from two to forty-six times their prescribed dose). The remaining five patients received excess treprostinil as a result of accidental bolus administration while in the process of changing syringes or tubing. Typical symptoms elicited were expected pharmacologic effects and included flushing, headache, hypotension, nausea, vomiting, and diarrhea.
The symptoms resolved with reduction of treprostinil dose or withholding treprostinil a short time. In only two cases did excess delivery of Treprostinil Injection produce an event of substantial hemodynamic concern (hypotension, near-syncope). No deaths occurred as a result of overdose.
One pediatric patient was accidentally administered 7.5 mg of treprostinil via a central venous catheter. Symptoms included flushing, headache, nausea, vomiting, hypotension, and seizure-like activity with loss of consciousness lasting several minutes. The patient subsequently recovered.
- 6.
Dosage Forms, Strengths, Composition, and Packaging
Table 1 Dosage Forms, Strengths, and Composition
| Route of Administration | Dosage Form/ Strength/Composition | Non-Medicinal Ingredients |
|---|---|---|
| Subcutaneous or Intravenous | Solution, 1 mg treprostinil per mL in 20 mL multi-use vials | Hydrochloric acid (to adjust pH), metacresol (3.0 mg), sodium chloride (5.3 mg), sodium citrate dihydrate (6.3 mg), sodium hydroxide (0.24 mg and to adjust pH), water for injection. |
| Subcutaneous or Intravenous | Solution, 2.5 mg treprostinil per mL in 20 mL multi-use vials | Hydrochloric acid (to adjust pH), metacresol (3.0 mg), sodium chloride (5.3 mg), sodium citrate dihydrate (6.3 mg), sodium hydroxide (0.32 mg and to adjust pH), water for injection. |
| Subcutaneous or Intravenous | Solution, 5 mg treprostinil per mL in 20 mL multi-use vials | Hydrochloric acid (to adjust pH), metacresol (3.0 mg), sodium chloride (5.3 mg), sodium citrate dihydrate (6.3 mg), sodium hydroxide (0.62 mg and to adjust pH), water for injection. |
| Subcutaneous or Intravenous | Solution, 10 mg treprostinil per mL in 20 mL multi-use vials | Hydrochloric acid (to adjust pH), metacresol (3.0 mg), sodium chloride (4.0 mg), sodium citrate dihydrate (6.3 mg), sodium hydroxide (1.2 mg and to adjust pH), water for injection. |
Packaging
Treprostinil Injection (treprostinil) for subcutaneous or intravenous use is supplied in:
20 mg/ 20 mL (1 mg/mL) Multidose vial: 20 mL clear glass vial with 20 mm dark grey rubber stopper and 20 mm yellow MT flip-off seal. Each carton contains one 20 mL vial.
50 mg/ 20 mL (2.5 mg/mL) Multidose vial: 20 mL clear glass vial with 20 mm dark grey rubber stopper and 20 mm blue MT flip-off seal. Each carton contains one 20 mL vial.
100 mg/ 20 mL (5 mg/mL) Multidose vial: 20 mL clear glass vial with 20 mm dark grey rubber stopper and 20 mm green MT flip-off seal. Each carton contains one 20 mL vial.
200 mg/ 20 mL (10 mg/mL) Multidose vial: 20 mL clear glass vial with 20 mm dark grey rubber stopper and 20 mm red MT flip-off seal. Each carton contains one 20 mL vial.
For the most recent information in the management of a suspected drug overdose, contact your regional poison control centre or Health Canada’s toll-free number, 1-844 POISON-X (1-844-764-7669).
7. Warnings and Precautions
General
The decision to initiate therapy with Treprostinil Injection should be based on the understanding that there is a high likelihood that subcutaneous or intravenous therapy with Treprostinil Injection will be needed for prolonged periods, possibly years, and the patient’s ability to administer Treprostinil Injection and care for an infusion system should be carefully considered.
As with any potent vasodilator, abrupt withdrawal or sudden large reductions in dosage of Treprostinil Injection may result in worsening of PAH symptoms. Avoid abrupt withdrawal of Treprostinil Injection if at all possible.
Although in clinical trials, no patient death from discontinuation of treprostinil was judged directly attributable to the interruption of the drug, 2 of 11 patients who abruptly discontinued subcutaneous treprostinil therapy died within 24 hours. Although their death may have been related to their deteriorating clinical condition, it seems most appropriate to wean patients from treprostinil. Only 3 of 55 (5%) patients with abrupt disruption of treprostinil developed increased symptoms of PAH, and no patients developed hemodynamic instability. In addition, among patients who discontinued treprosinil abruptly, no relationship has been established between abrupt discontinuation and rebound pulmonary hypertension.
Carcinogenesis and Genotoxicity
Long-term studies in humans have not been performed to evaluate the carcinogenic potential of treprostinil (see 16 Non-Clinical Toxicology for results from animal studies).
Hepatic/Biliary/Pancreatic
An acute study of treprostinil administered subcutaneously at a dose of 10 ng/kg/min for 150 minutes was conducted in nine patients with portopulmonary hypertension and stable, mild or moderate hepatic dysfunction. Treprostinil was well tolerated and improved cardiopulmonary hemodynamics. Hepatic dysfunction reduced plasma clearance of treprostinil by up to 80% compared to healthy adult subjects primarily by lowering the volume of distribution without affecting plasma half-life.
Treprostinil Injection should be increased more conservatively in patients with hepatic dysfunction, because such patients will likely be exposed to greater systemic concentrations relative to patients with normal hepatic function. These patients should be closely monitored for signs and symptoms or emergence of adverse reactions due to excess Treprostinil Injection. Treprostinil has not been studied in patients with severe hepatic dysfunction.
Pulmonary Veno-Occlusive Disease
Cases of pulmonary edema have been reported with vasodilators when used in patients with pulmonary veno-occlusive disease. Consequently, if signs of pulmonary edema occur when Treprostinil Injection is administered in patients with PAH, the possibility of pulmonary veno-occlusive disease should be considered.
Renal
No studies have been performed in patients with renal impairment. Treprostinil is not excreted to any significant degree by the kidney, however, its metabolites are excreted mainly by the kidney. Based on the individual patient dose titration recommended for Treprostinil Injection, doses of Treprostinil Injection should be increased more conservatively in patients with renal insufficiency.
Risk of Catheter-Related Blood Stream Infections
Chronic intravenous infusions of Treprostinil Injection are delivered using an indwelling central venous catheter. This route is associated with the risk of blood stream infections (BSIs) and sepsis, which may be fatal.
Therefore, continuous subcutaneous infusion (undiluted) is the preferred mode of administration.
7.1 Special Populations
7.1.1 Pregnancy
The extent of exposure in pregnancy during clinical trials is very limited. There are no adequate and well controlled studies in pregnant women. No developmental toxicity was seen in rats at any dose of treprostinil up to 900 ng/kg/min and in rabbits at 50 ng/kg/min. In pregnant rabbits, developmental toxicity characterized by minimal increases in fetal skeletal variations per litter was observed at doses of 150 and 300 ng/kg/min and was associated with maternal toxicity.
7.1.2 Breastfeeding
It is not known whether treprostinil is excreted in human milk. Because many drugs are excreted in human milk, and because of their potential for affecting the nursing infant adversely, a decision should be made whether to discontinue nursing or to discontinue the drug, taking into account the importance of the drug to the mother.
7.1.3 Pediatrics
Pediatrics (<16 years of age): Based on the data submitted and reviewed by Health Canada, the safety and efficacy of treprostinil in pediatric patients has not been established; therefore, Health Canada has not authorized an indication for pediatric use (see 1.1 Pediatrics). Clinical studies of treprostinil did not include sufficient numbers of patients aged <16 years to determine whether they respond differently from older patients.
7.1.4 Geriatrics
Geriatrics (>65 years of age): Clinical studies of treprostinil did not include sufficient numbers of patients aged 65 years and over to determine whether they respond differently from younger patients. In general, dose selection for an elderly patient should be cautious, reflecting the greater frequency of decreased hepatic, renal or cardiac function, and of concomitant disease or other drug therapy.
8. Adverse Reactions
8.1 Adverse Reaction Overview
Interpretation of adverse events (AEs) reported during clinical trials should be undertaken with an awareness of expected events attributable to the progression of the underlying disease, to Treprostinil Injection, and/or to the drug delivery system.
Interpretation of adverse events is complicated by the clinical features of PAH, which are similar to some of the pharmacological effects of treprostinil (e.g., dizziness, syncope). Adverse events probably related to the underlying disease include dyspnea, fatigue, chest pain, right ventricular heart failure, and pallor. During clinical trials with subcutaneous infusion of treprostinil, infusion site pain and reaction were the most common adverse events among those treated with treprostinil. Infusion site reaction was defined as any local adverse event other than pain or bleeding/bruising at the infusion site and included symptoms such as erythema, induration or rash.
Adverse reactions included headache, diarrhea, vomiting, jaw pain, swelling/edema, flushing/vasodilatation, muscle or joint pain, low systemic blood pressure, pain in extremities and nausea, and these are generally considered to be related to the pharmacologic effects of treprostinil, whether administered subcutaneously or intravenously.
8.2 Clinical Trial Adverse Reactions
Clinical trials are conducted under very specific conditions. Therefore, the frequencies of adverse reactions observed in the clinical trials may not reflect the frequencies observed in clinical practice and should not be compared to the frequencies reported in the clinical trials of another drug. Adverse drug reaction information from clinical trials is useful for identifying drug-related adverse events and for approximating rates.
Adverse Reactions During Chronic Treatment
In an effort to separate the adverse reactions on treprostinil from those of the underlying disease, Table 2 lists adverse events that occurred at a rate greater than 1% in PAH patients participating in placebo-controlled trials of subcutaneous treprostinil.
Table 2 Frequency of Adverse Events Regardless of Attribution Occurring in >1% of Patients with PAH in Placebo-Controlled Studies of Subcutaneous Treprostinil
| Treprostinil (N=236) N (%) | Placebo (N=233) N (%) | ||||||
|---|---|---|---|---|---|---|---|
| Treprostinil (N=236) N (%) | Placebo (N=233) N (%) | ||||||
| Treprostinil (N=236) N (%) | Placebo (N=233) N (%) | ||||||
| OCCURRENCE MORE COMMON WITH TREPROSTINIL INJECTION | |||||||
| Skin and Appendages | |||||||
| Infusion site pain | 200 (84.7) | 62 (26.6) | |||||
| Infusion site reaction | 196 (83.1) | 62 (26.6) | |||||
| Rash | 32 (13.6) | 26 (11.2) | |||||
| Pruritus | 19 (8.1) | 15 (6.4) | |||||
| Contact Dermatitis | 3 (1.3) | 1 (0.4) | |||||
| Sweating | 3 (1.3) | 1 (0.4) | |||||
| General (Body as Whole) | |||||||
| Headache | 64 (27.1) | 54 (23.2) | |||||
| Jaw pain | 31 (13.1) | 11 (4.7) | |||||
| Pain | 28 (11.9) | 25 (10.7) | |||||
| Infection | 21 (8.9) | 20 (8.6) | |||||
| Asthenia | 11 (4.7) | 7 (3.0) | |||||
| Flu Syndrome | 11 (4.7) | 9 (3.9) | |||||
| Overdose | 3 (1.3) | 0 (0.0) | |||||
| Injection Site Reaction | 3 (1.3) | 0 (0.0) | |||||
| Gastrointestinal (Digestive) | |||||||
| Diarrhea | 58 (24.6) | 36 (15.5) | |||||
| Nausea | 52 (22.0) | 41 (17.6) | |||||
| Anorexia | 11 (4.7) | 4 (1.7) | |||||
| Nausea and vomiting | 7 (3.0) | 2 (0.9) | |||||
| Melena | 5 (2.1) | 0 (0.0) | |||||
| Rectal Hemorrhage | 3 (1.3) | 0 (0.0) | |||||
| Cardiovascular | |||||||
| Hypotension | 9 (3.8) | 6 (2.6) | |||||
| Tachycardia | 4 (1.7) | 3 (1.3) | |||||
| Palpitation | 3 (1.3) | 2 (0.9) | |||||
| Hematologic and Lymphatic | 3 (1.3) | 3 (1.3) | |||||
| Anemia | |||||||
| Metabolic and Nutritional | |||||||
| Edema | 21 (8.9) | 6 (2.6) | |||||
| Hypokalemia | 5 (2.1) | 0 (0.0) | |||||
| Gout | 3 (1.3) | 1 (0.4) | |||||
| Dehydration | 3 (1.3) | 0 (0.0) | |||||
| Musculoskeletal | 3 (1.3) | 1 (0.4) | |||||
| Myalgia | |||||||
| Neurological/Nervous | |||||||
| Vasodilatation | 25 (10.6) | 11 (4.7) | |||||
| Dizziness | 21 (8.9) | 19 (8.2) | |||||
| Insomnia | 14 (5.9) | 8 (3.4) | |||||
| Anxiety | 7 (3.0) | 6 (2.6) | |||||
| Paresthesia | 3 (1.3) | 2 (0.9) | |||||
| Respiratory | |||||||
| Epistaxis | 10 (4.2) | 4 (1.7) | |||||
| Rhinitis | 5 (2.1) | 5 (2.1) | |||||
| Hypoxia | 4 (1.7) | 1 (0.4) | |||||
| Urogenital | 4 (1.7) | 3 (1.3) | |||||
| Urinary Tract Infection | |||||||
| OCCURRENCE MORE COMMON WITH PLACEBO | |||||||
| Skin and Appendages | 79 (33.5) | 102 (43.8) | |||||
| Infusion site bleed/bruise | |||||||
| Hematologic and Lymphatic | 9 (3.8) | 27 (11.6) | |||||
| Ecchymosis | |||||||
| Body | |||||||
| Chest Pain | 10 (4.2) | 20 (8.6) | |||||
| Abdominal Pain | 8 (3.4) | 10 (4.3) | |||||
| Back Pain | 6 (2.5) | 11 (4.7) | |||||
| Fever | 6 (2.5) | 10 (4.3) | |||||
| Cellulitus | 3 (1.3) | 3 (1.3) | |||||
| Malaise | 2 (0.8) | 3 (1.3) | |||||
| Viral Infection | 1 (0.4) | 3 (1.3) | |||||
| Neck Pain | 2 (0.8) | 5 (2.1) | |||||
| Cardiovascular | |||||||
| Heart Failure | 7 (3.0) | 17 (7.3) | |||||
| Hemorrhage | 7 (3.0) | 13 (5.6) | |||||
| Syncope | 7 (3.0) | 12 (5.2) | |||||
| Bradycardia | 3 (1.3) | 3 (1.3) | |||||
| Gastrointestinal (Digestive) | |||||||
| Vomiting | 12 (5.1) | 14 (6.0) | |||||
| Dyspepsia | 3 (1.3) | 6 (2.6) | |||||
| Metabolic and Nutritional | 11 (4.7) | 16 (6.9) | |||||
| Peripheral Edema | |||||||
| Neurological/Nervous | |||||||
| Depression | 3 (1.3) | 6 (2.6) | |||||
| Nervousness | 1 (0.4) | 3 (1.3) | |||||
| Respiratory | |||||||
| Pharyngitis | 13 (5.5) | 21 (9.0) | |||||
| Cough | 7 (3.0) | 19 (8.2) | |||||
| Dyspnea | 8 (3.4) | 19 (8.2) | |||||
| Sinusitis | 4 (1.7) | 9 (3.9) | |||||
| Pulmonary Hypertension | 4 (1.7) | 6 (2.6) | |||||
| Hemoptysis | 4 (1.7) | 5 (2.1) | |||||
| Bronchitis | 2 (0.8) | 6 (2.6) | |||||
| Urogenital | 2 (0.8) | 3 (1.3) | |||||
| Hematuria | |||||||
| Musculoskeletal | |||||||
| Leg Cramps | 2 (0.8) | 5 (2.1) | |||||
| Arthralgia | 2 (0.8) | 3 (1.3) | |||||
Adverse Event Description as COSTART Preferred Term
Table 3 lists all adverse reactions reported in controlled clinical trials of patients with PAH, that were significantly more frequently encountered in the subcutaneous treprostinil group than in the placebo group, regardless of attribution.
Table 3 Adverse Reactions Occurring Significantly (p<0.1) More Frequently in the Subcutaneous Treprostinil Group than in the Placebo Group, Regardless of Attributability
| Adverse Reaction Description, as COSTART Preferred Term | Number of Events Treprostinil Group / Placebo Group | p-value |
|---|---|---|
| Any adverse reaction | 231 / 218 | 0.0173 |
| Infusion site pain | 200 / 62 | <0.0001 |
| Infusion site reaction | 196 / 62 | <0.0001 |
| Diarrhea | 58 / 36 | 0.0091 |
| Jaw pain | 31 / 11 | 0.0010 |
| Vasodilatation | 25 / 11 | 0.0127 |
| Edema | 21 / 6 | 0.0026 |
| Anorexia | 11 / 4 | 0.0592 |
| Epistaxis | 10 / 4 | 0.0904 |
| Nausea and vomiting | 7 / 2 | 0.0909 |
| Hypokalemia | 5 / 0 | 0.0316 |
| Melena | 5 / 0 | 0.0316 |
Adverse Events Attributable to the Drug Delivery System: In controlled studies of treprostinil administered subcutaneously, there were no reports of infection related to the drug delivery system. There were 187 infusion system complications reported in 28% of patients (23% treprostinil, 33% placebo); 173 (93%) were pump related and 14 (7%) related to the infusion set. Eight of these patients (4 treprostinil, 4 placebo) reported non-serious adverse events resulting in infusion system complications. Adverse events resulting from problems with the delivery system did not lead to clinical instability or rapid deterioration, although in some cases PAH symptoms reappeared. These events were generally resolved by correcting the delivery system pump or infusion set problem such as replacing the syringe or battery, reprogramming the pump, or straightening a crimped infusion line.
Adverse events resulting from problems with the delivery system did not lead to clinical instability or rapid deterioration. In addition to these adverse events due to the drug delivery system during subcutaneous administration, the following adverse events may be attributable to the IV mode of infusion including arm swelling, paresthesias, hematoma and pain.
There are a limited number of clinical studies with treprostinil administered via central venous infusion. The overall adverse event profile in these intravenous studies is similar to that of treprostinil administered subcutaneously, as would be expected based on the established bioequivalence of subcutaneous and intravenous routes of administration. However, as with any chronic indwelling central venous catheter, there are risks associated with delivery of therapy by this route. These risks include pain at the catheter insertion site, local infection, sepsis, thrombus formation and subsequent line occlusion, and malfunctions in the delivery system resulting in an inadvertent bolus of or a reduction in treprostinil which could produce symptoms related to excess or insufficient treprostinil, respectively.
In an open-label study of intravenous treprostinil (n=47) there were seven catheter-related line infections during approximately 35 patient years, or about 1 blood stream infection (BSI) event per 5 years of use. A Centers for Disease Control survey of seven sites that used intravenous treprostinil for the treatment of PAH found approximately 1 BSI (defined as any positive blood culture) event per 3 years of use.
Among patients randomized in a 12-week placebo-controlled study in India to either intravenous treprostinil (n=30) or placebo (n=15), vomiting, headache, diarrhea, jaw pain and extremity pain were more common in patients treated with treprostinil than placebo. Serious AEs were no more common in the treprostinil group than the placebo group, and included sepsis, congestive heart failure, pulmonary embolism, thrombophlebitis, catheter related complications, pseudomonal sepsis and pseudomonas infection.
8.5. Post-Market Adverse Reactions
In addition to adverse events reported from clinical trials, the following events have been identified during post-approval use of treprostinil. Because they are reported voluntarily from a population of unknown size, estimates of frequency cannot be made. The following events have been chosen for inclusion because of a combination of their seriousness, frequency of reporting, and potential connection to treprostinil. These events are thrombophlebitis associated with peripheral intravenous infusion, thrombocytopenia, bone pain, pruritus, dizziness, arthralgia, myalgia, and muscle spasm.
Treprostinil inhibits platelet aggregation and increases the risk of bleeding. In addition, generalized rashes, sometimes macular or papular in nature, and cellulitis have been infrequently reported.
9. Drug Interactions
9.2 Drug Interactions Overview
In clinical studies, no untoward clinical manifestations have been observed in patients in whom treprostinil was used concurrently with the following classes of drugs: anticoagulants, diuretics, cardiac glycosides, calcium channel blockers, analgesics, antipyretics, nonsteroidal anti-inflammatory drugs, opioids, and corticosteroids.
9.3 Drug-Behavior Interactions
Interaction potential with alcohol has not been established.
9.4 Drug-Drug Interactions
Antihypertensive Agents or other Vasodilators
Additional reductions in blood pressure may occur when Treprostinil Injection is administered with diuretics, antihypertensive agents, or other vasodilators.
Anticoagulants and Antiplatelet Agents
When antiplatelet agents or anticoagulants are used concomitantly with Treprostinil Injection there is the potential for increased risk of bleeding due to the antiplatelet effect of treprostinil. However, patients receiving treprostinil in clinical trials were maintained on anticoagulants without evidence of increased bleeding. Treprostinil investigated in healthy subjects had no effect in vivo on warfarin pharmacodynamics as measured by the effect on INR. Treprostinil also had no effect on pharmacokinetics of either the R- or S-enantiomer of warfarin.
Effect of Cytochrome P450 Inhibitors and Inducers on Treprostinil
Human pharmacokinetic studies with an oral formulation of treprostinil (treprostinil diethanolamine) indicated that co-administration of the cytochrome P450 (CYP) 2C8 enzyme inhibitor gemfibrozil increases exposure (both Cmax and AUC) to treprostinil. Treprostinil Injection dose reduction should be considered.
Co-administration of the CYP2C8 enzyme inducer rifampin decreases exposure to treprostinil. It has not been determined if the safety and efficacy of treprostinil by the parenteral (subcutaneously or intravenously) route are altered by inhibitors or inducers of CYP2C8. Treprostinil Injection dose increases should be considered.
Modest interaction was observed between treprostinil and furosemide. Treprostinil Injection dose reduction in patients receiving furosemide is not recommended, although patients should be monitored for excess adverse effects of Treprostinil Injection.
10. Clinical Pharmacology
10.1 Mechanism of Action
Treprostinil is a tricyclic benzindene analogue of prostacyclin (PGI2). The major pharmacologic actions of treprostinil are direct vasodilation of pulmonary and systemic arterial vascular beds, and inhibition of platelet aggregation. In animals, the vasodilatory effects reduce right and left ventricular afterload and increase cardiac output and stroke volume. The effect of treprostinil on heart rate in animals varies with dose. No major effects on cardiac conduction have been observed.
10.2 Pharmacodynamics
Clinical Trials in Pulmonary Arterial Hypertension (PAH)
Hemodynamic Effects: Acute infusion of treprostinil at 10 ng/kg/min intravenously for 75 minutes followed by a 10 ng/kg/min infusion subcutaneously for 150 minutes, in patients with primary pulmonary hypertension produced increases in cardiac index (CI) and mixed venous oxygen saturation (SvO2), and decreases in mean pulmonary arterial pressure (PAPm), mean right atrial pressure (RAPm) and pulmonary vascular resistance indexed (PVRI), with little effect on mean systemic arterial pressure (SAPm), or heart rate (HR).
Chronic continuous, subcutaneous infusion of treprostinil in NYHA Class II, III, or IV patients with PAH was studied in two identical, 12-week, double-blind, placebo-controlled, multicenter, parallel-group, randomized trials comparing treprostinil plus conventional therapy to conventional therapy alone.
Dosage of treprostinil averaged 9.3 ng/kg/min at Week 12.
The hemodynamic effects from the two placebo-controlled studies are shown in Table 4. The hemodynamic effects after chronic therapy with treprostinil were generally consistent with the pharmacological effects seen acutely. There were statistically significant increases in CI and SvO2, and statistically significant decreases in PAPm, RAPm, PVRI, and SVRI in patients treated with treprostinil for 12 weeks compared to patients treated with placebo. Heart rate and SAPm were unchanged. In patients with pulmonary hypertension, elevated RAPm and PAPm, and reduced CO and SvO2 are predictive of mortality.
Table 4 Hemodynamics During Chronic Subcutaneous Administration of Subcutaneous Treprostinil in Patients with PAH
| Baseline | Mean Change from Baseline at Week 12 | |||||||||
|---|---|---|---|---|---|---|---|---|---|---|
Hemodynamic Parameter | Treprostinil (N=204-231) | Placebo (N=215-235) | Treprostinil (N=163-199) | Placebo (N=182-215) | ||||||
| CI (L/min/m2) | 2.37 ± 0.06 | 2.24 ± 0.05 | +0.12 ± 0.04* | -0.06 ± 0.04 | ||||||
| PAPm (mmHg) | 61.8 ± 1.16 | 59.9 ± 0.96 | -2.3 ± 0.51* | +0.7 ± 0.58 | ||||||
| RAP (mmHg) | 10.3 ± 0.38 | 10.0 ± 0.39 | -0.5 ± 0.36* | +1.4 ± 0.33 | ||||||
PVRI (mmHg/L/min/m2) | 26.51 ± 0.97 | 25.11 ± 0.87 | -3.54 ± 0.64* | +1.20 ± 0.57 | ||||||
SVRI (mmHg/L/min/m2) | 37.87 ± 1.05 | 39.23 ± 1.02 | -3.54 ± 0.96* | -0.80 ± 0.85 | ||||||
| SvO2 (%) | 61.5 ± 0.70 | 60.2 ± 0.77 | +2.0 ± 0.76* | -1.4 ± 0.65 | ||||||
| SAPm (mmHg) | 89.6 ± 0.92 | 90.7 ± 0.89 | -1.7 ± 0.86 | -1.0 ± 0.91 | ||||||
| HR (bpm) | 82.4 ± 0.83 | 82.1 ± 0.97 | -0.5 ± 0.80 | -0.8 ± 0.74 | ||||||
*Denotes statistically significant difference between treprostinil and placebo, p≤0.0005.
CI, cardiac index; PAPm, mean pulmonary arterial pressure; PVRI, pulmonary vascular pressure indexed; RAPm, mean right atrial pressure; SAPm, mean systemic arterial pressure; SVRI, systemic vascular resistance indexed; SvO2, mixed venous oxygen saturation; HR, heart rate.
10.3 Pharmacokinetics
Table 5 provides data from a randomized, two-period, cross-over study of treprostinil in healthy subjects. In this study, subcutaneous and intravenous administration of treprostinil (10 ng/kg/min) for 72 hours demonstrated bioequivalence at steady-state, between 48 and 72 hours.
Table 5 Summary of Pharmacokinetic Parameters of Treprostinil in Healthy Subjects
| Route of Treprostinil Administration (10 ng/kg/min) | Cmax ss (ng/mL) | t½ (h) Geom. Mean | t½ (h) Mean | AUCss (hr*ng/mL) | Clearance mL/kg/h | Volume of distribution (L/kg) |
|---|---|---|---|---|---|---|
| Subcutaneous | 1.39 | 4.13 | 4.61 | 27.63 | 550.8 | 3.28 |
| Intravenous | 1.47 | 3.45 | 4.41 | 25.69 | 565.8 | 2.82 |
Steady-state (ss) comparisons were made based on extensive plasma sampling between 48 and 72 hours.
In a [14C] treprostinil mass balance and metabolic fate study in healthy subjects, 78.6% and 13.4% of the subcutaneous radioactive dose were recovered in the urine and feces, respectively, over a period of 224 hours. Five metabolites were detected in the urine, ranging from 10.2% to 15.5% of the dose administered. These five metabolites accounted for a combined total of 64.4%. Three metabolites are products of oxidation of the 3-hydroxyloctyl side chain, one is glucuronide conjugate (treprostinil glucuronide) and one is unidentified. Only 3.7% of the dose was recovered in the urine as unchanged parent drug.
In a chronic pharmacokinetic study in healthy subjects with chronic subcutaneous treprostinil doses ranging from 2.5 to 15 ng/kg/min, steady-state plasma treprostinil concentrations achieved peak levels twice (at 1 a.m. and 10 a.m., respectively) and achieved trough levels twice (at 7 a.m. and 4 p.m., respectively). The peak concentrations were ~20% to 30% higher than trough concentrations. Dose adjustments are not deemed to be necessary due to diurnal variation.
Absorption
Treprostinil is rapidly and completely absorbed after subcutaneous infusion, with an absolute bioavailability approximating 100%. Steady-state concentrations occurred in approximately 10 hours. Concentrations in patients treated with an average dose of 9.3 ng/kg/min were approximately 2 mcg/L.
Distribution
The volume of distribution of the drug in the central compartment is approximately 14L/70 kg ideal body weight. Treprostinil at in vitro concentrations ranging from 330-10,000 µg/L was 91% bound to human plasma protein.
Metabolism
Treprostinil is substantially metabolized by the liver, but the precise enzymes responsible are unknown. Five metabolites have been described (HU1 through HU5). The biological activity and metabolic fate of these metabolites are unknown. The chemical structure of HU1 is unknown. HU5 is the glucuronide conjugate of treprostinil. The other metabolites are formed by oxidation of the 3-hydroxyoctyl side chain (HU2) and subsequent additional oxidation (HU3) or dehydration (HU4). Based on the results of in vitro human hepatic cytochrome P450 studies, treprostinil does not inhibit CYP-1A2, 2C9, 2C19, 2D6, 2E1, or 3A. Whether treprostinil induces these enzymes has not been studied.
Elimination
The elimination of treprostinil is biphasic, with a terminal half-life of approximately 4 hours. Approximately 79% of an administered dose is excreted in the urine as unchanged drug (4%) and as the identified metabolites (64%). Approximately 13% of a dose is excreted in the feces. Systemic clearance is approximately 30 L/h for a 70 kg ideal body weight person.
Special Populations and Conditions
- Hepatic Insufficiency: No formal pharmacokinetic studies were conducted in patients with hepatic impairment (see 7 Warnings and Precautions).
- Renal Insufficiency: No formal pharmacokinetic studies were conducted in patients with renal impairment (see 7 Warnings and Precautions).
- Obesity: Obese subjects (BMI >30.0 kg/m2) clear treprostinil at a slower rate. Doses of treprostinil are increased from very low initial doses to doses that improve disease symptoms while minimizing adverse effects. No formal dose adjustments due to obesity are required. Dose according to 4.2 Recommended Dose and Dosage Adjustment.
- Pediatric patients: Clinical studies of treprostinil did not include sufficient numbers of patients aged <16 years to determine whether they respond differently from older patients.
- Storage, Stability, and Disposal
Treprostinil Injection should be stored at room temperature at 15°C to 30°C. The products are to be stored in the original carton packaging and protected from light. A single vial of Treprostinil Injection should be used for no more than 30 days after the initial puncture of the rubber stopper.
Treprostinil Injection can be administered without further dilution for subcutaneous administration, or diluted for intravenous infusion with Sterile Water for Injection, or 0.9% Sodium Chloride Injection prior to administration to concentrations as low as 0.004 mg/mL. See Table 6 for storage and administration time limits.
Table 6 Storage
| Route | Diluent | Storage limits | Administration limits |
|---|---|---|---|
| SC | None | Per vial label | 72 hours at 37°C |
| IV | Sterile water for injection 0.9% Sodium Chloride for injection | 4 hours at room temperature or 24 hours refrigerated | 48 hours at 40°C |
12. Special Handling Instructions
Avoid contact with skin or eyes. For skin contact, wash affected area immediately with soap and water and contact physician. For eye contact, flush eyes immediately with large amounts of water and contact physician.
Part 2: Scientific Information
13. Pharmaceutical Information
Drug Substance
Non-proprietary name of the drug substance: Treprostinil (treprostinil sodium, the soluble sodium salt of treprostinil, is formed during the finished product manufacturing process)
Chemical name: Acetic acid, [[(1R,2R,3aS,9aS)-2,3,3a,4,9,9a-hexahydro-2-hydroxy-1-[(3S)-3- hydroxyoctyl]-1H-benz[f]inden-5-yl]oxy]-monohydrate
[(1R,2R,3aS,9aS)-2-Hydroxy-1-((3S)-3-hydroxyoctyl)-2,3,3a,4,9,9ahexahydro-1H cylopent[b]naphthalen-5-yl]oxy] acetate monohydrate.
Molecular formula and molecular mass: C23H34O5 390.52 g/mol
Structural formula:
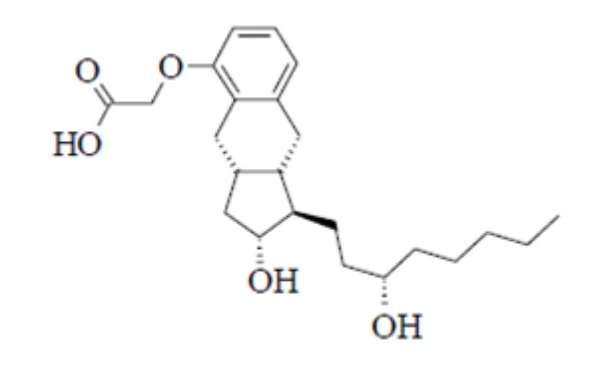
Physicochemical properties:
Description: White to off-white powder
Solubility: Freely soluble in methanol. Aqueous solubility of treprostinil at different pH buffers is summarized below:
| Buffer pH | Observation |
| 1.2 | Practically insoluble |
| 6.0 | Practically insoluble |
| 8.0 | Sparingly soluble |
pKa: 4.5
Partition Coefficient: 4
Melting Range: 123.3°C
14. Clinical Trials
14.1 Clinical Trials by Indication
Treatment of Pulmonary Arterial Hypertension in NYHA Class II and IV Patients Who Do Not Respond Adequately to Conventional Therapy
Table 7 Summary of Patient Demographics for Study P01:04/05 in Patients with PAH
| Study # | Trial design | Dosage, route of administration and duration | Study subjects (n=number) | Mean age (Range) | Gender |
|---|---|---|---|---|---|
P01:04 and P01:05 | 12-week, multicenter, randomized, double-blind, parallel studies comparing continuous subcutaneous treprostinil to placebo | Average 9.3 ng/kg/min continuous subcutaneous injection at 12 weeks | 470 | 45 (9-75) years | 81% Female |
PAH, Pulmonary Arterial Hypertension
Two 12-week, multicenter, randomized, double-blind studies compared continuous subcutaneous infusion of treprostinil Injection to placebo in a total of 470 patients with NYHA Class II (11%), III (81%), or IV (7%) pulmonary arterial hypertension (PAH). PAH was idiopathic/heritable in 58% of patients, associated with connective tissue diseases in 19%, and the result of congenital systemic-to-pulmonary shunts in 23%. The mean age was 45 (range 9 to 75 years). About 81% were female and 84% were Caucasian. Pulmonary arterial hypertension had been diagnosed for a mean of 3.8 years. The primary endpoint of the studies was change in 6-minute walking distance, a standard measure of exercise capacity. There were many assessments of symptoms related to heart failure, but local discomfort and pain associated with subcutaneous treprostinil may have substantially unblinded those assessments. The 6-minute walking distance and an associated subjective measurement of shortness of breath during the walk (Borg dyspnea score) were administered by a person not participating in other aspects of the study. Treprostinil was administered as a subcutaneous infusion, and the dose averaged
9.3 ng/kg/min at Week 12. Few subjects received doses > 40 ng/kg/min. Background therapy, determined by the investigators, could include anticoagulants, oral vasodilators, diuretics, digoxin, and oxygen but not an endothelin receptor antagonist or epoprostenol.
Table 8 Results of Study P01:04/05 in Patients with PAH
| Primary Endpoint | Treatment Effect (Subcutaneous Treprostinil– Placebo) mean ± SE (meters) | p-value |
|---|---|---|
Six Minute Walk Test NYHA Class III NYHA Class IV | 21.63 ± 7.69 56.41 ± 25.55 | 0.0051 0.0278 |
Clinical Effects: As the two 12-week studies were identical in design and conducted simultaneously, results were analyzed both pooled and individually. Exercise capacity, as measured by the Six-Minute
Walk Test, improved significantly in Class II, III, and IV patients receiving continuous subcutaneous treprostinil plus conventional therapy (N=232) for 12 weeks, with a median increase of 10 meters in this group compared to those receiving conventional therapy plus placebo (N=236) (p=0.0064). Table 8 specifies the improvements in Six-Minute Walk distance at Week 12 for treprostinil patients with NYHA Class III and IV PAH, for which treprostinil is indicated. Improvements, although not statistically significant, were apparent as early as Week 6 of therapy. Increases in exercise capacity were accompanied by statistically significant improvements in dyspnea and fatigue, as measured by the Dyspnea-Fatigue Rating and Borg Scale. Signs and symptoms of PAH also improved, as did the Physical Dimension component of a Quality of Life Scale. Treprostinil was shown to be effective for the treatment of PAH, either primary (PPH), or secondary to the scleroderma spectrum of diseases or associated with congenital systemic-to-pulmonary shunts (repaired or unrepaired), in NYHA Class III and IV patients who did not respond adequately to conventional therapy.
Hemodynamic Effects: As shown previously in Table 4 and 10.2 Pharmacodynamics, hemodynamic effects after chronic subcutaneous therapy with treprostinil were generally consistent with the pharmacological effects seen acutely. There were statistically significant increases in CI and SvO2, and statistically significant decreases in PAPm, RAPm, PVRI, and SVRI in patients treated with treprostinil for 12 weeks compared to patients treated with placebo. Heart rate and SAPm were unchanged. In patients with pulmonary hypertension, elevated RAPm and PAPm, and reduced CO and SvO2 are predictive of mortality.
14.2 Comparative Bioavailability Studies
Study REM01:14 was a randomized, open-label, two-period crossover bioequivalence study comparing intravenous versus subcutaneous administration of treprostinil in healthy adult subjects. The objective of the study was to demonstrate steady-state bioequivalence.
Subjects were to receive 72 hours of treprostinil infusion (10 ng/kg/min) by both the intravenous and subcutaneous routes for pharmacokinetic comparisons. Steady-state comparisons were made based on extensive plasma sampling between 48 and 72 hours, for each respective route of administration. A total of 55 adult subjects (60% male, mean age 36.2 years mean body weight was 73.9 kg) received study drug and were included in the safety population for the study. Fifty-one subjects received at least 24 hours of treprostinil infusion by both routes and were included in the primary pharmacokinetic analyses.
The primary analysis results are shown in Table 9 and Table 10.
Table 9 Summary of Primary Steady State Pharmacokinetic Parameters (n=51)
| Parameter | Statistic | IV | SC | Bioequivalence Comparison1 | |||||
|---|---|---|---|---|---|---|---|---|---|
AUCss (hr*ng/mL) | Geom LS Mean | 25.67 | 27.63 | 92.9 (89.8, 96.1) | |||||
| Geom Mean | 25.69 | 27.63 | |||||||
| CV (%) | 22.00 | 16.22 | |||||||
Cmaxss (ng/mL) | Geom LS Mean | 1.47 | 1.39 | 106.0 (99.4, 113.0) | |||||
| Geom Mean | 1.47 | 1.39 | |||||||
| CV (%) | 37.51 | 16.06 | |||||||
SS, Steady State
1 Point Estimate (90% Confidence Interval)
The 90% confidence intervals for the ratios of adjusted geometric means (IV/SC) are well within the bioequivalence boundaries (confidence intervals between 80% – 125%) for both AUCss and Cmaxss. Therefore, intravenous and subcutaneous treprostinil are bioequivalent at steady state.
Other pharmacokinetic assessments included AUC0-96h, AUCinf, Cmax, observed time to maximal plasma concentration (Tmax), apparent plasma clearance (CL), apparent volume of distribution (Vz), elimination rate constant of the terminal disposition phase (λz), and elimination half-life (T1/2). As shown in Table 10, these parameters were comparable between the two routes of administration. Of note, the apparent mean elimination half-life following cessation of IV infusion of treprostinil was 4.4 hours compared to 4.6 hours for SC.
Table 10 Summary of Pharmacokinetic Parameters Related to the Full Profile
| IV Infusion (N=51) | |||||||
|---|---|---|---|---|---|---|---|
| Parameter | Geom. Mean | CV (%) | Mean | SD | Median | Min | Max |
| AUCinf (hr*ng/mL) | 76.37 | 16.32 | 77.38 | 12.63 | 76.21 | 55.85 | 102.66 |
| AUC0-96h (hr*ng/mL) | 76.25 | 16.32 | 77.26 | 12.61 | 76.19 | 55.80 | 102.61 |
| Cmax (ng/mL) | 1.68 | 51.57 | 1.82 | 0.94 | 1.62 | 0.95 | 6.73 |
| Tmax (hr) | 21.29 | 74.96 | 36.39 | 27.28 | 51.00 | 2.00 | 69.00 |
| λz (1/hr) | 0.201 | 51.80 | 0.238 | 0.123 | 0.231 | 0.030 | 0.503 |
| T1/2 (hr) | 3.45 | 90.21 | 4.41 | 3.98 | 3.00 | 1.38 | 23.36 |
| CL (mL/min/kg) | 9.43 | 16.61 | 9.56 | 1.59 | 9.45 | 7.01 | 12.89 |
| Vz (L/Kg) | 2.82 | 88.29 | 3.65 | 3.22 | 2.68 | 0.95 | 16.76 |
| SC Infusion (N=51) | |||||||
|---|---|---|---|---|---|---|---|
| Parameter | Geom. Mean | CV (%) | Mean | SD | Median | Min | Max |
| AUCinf (hr*ng/mL) | 78.44 | 15.06 | 79.31 | 11.95 | 80.10 | 58.94 | 110.26 |
| AUC0-96h (hr*ng/mL) | 78.34 | 15.10 | 79.21 | 11.96 | 80.05 | 58.91 | 110.22 |
| Cmax (ng/mL) | 1.41 | 15.70 | 1.43 | 0.22 | 1.45 | 1.01 | 1.93 |
| Tmax (hr) | 36.47 | 46.61 | 50.27 | 23.43 | 63.00 | 2.00 | 69.05 |
| lz (1/hr) | 0.168 | 37.21 | 0.182 | 0.068 | 0.182 | 0.039 | 0.367 |
| T1/2 (hr) | 4.13 | 59.04 | 4.61 | 2.72 | 3.82 | 1.89 | 18.00 |
| CL (mL/min/kg) | 9.18 | 14.95 | 9.28 | 1.39 | 8.99 | 6.53 | 12.22 |
| Vz (L/Kg) | 3.28 | 65.22 | 3.71 | 2.42 | 3.04 | 1.63 | 16.54 |
16. Non-Clinical Toxicology
General Toxicology: The preclinical toxicology of treprostinil has been extensively evaluated in a series of in vitro and in vivo genetic toxicology studies, reproductive toxicology studies in rats and rabbits, and single and repeated dose toxicity studies in mice, rats and dogs.
Acute Toxicity Studies
Treprostinil has low oral and intravenous acute toxicity in mice and rats (Table 11).
Table 11 Incidence of Death in Acute Toxicity Studies
| Species | No. per Group | Dose (mg/kg) | Route | MLD mg/kg |
|---|---|---|---|---|
| Mouse | 10 M, 10 F | 150, 300 | oral | 150 |
| 20 M, 20 F | 0 | |||
| 10 M, 10 F | 0, 100 | i.v. | 100 | |
| Rat | 10 M, 10 F | 75, 150, 300 | oral | 114 M, 92 F* |
| 20 M, 20 F | 0 | |||
| 10 M, 10 F | 50, 100 | i.v. | 50 | |
| 20 M, 20 F | 0 |
MLD, Minimum lethal dose *Median lethal dose i.v., intravenous
In acute subcutaneous toxicity studies in rats and dogs, the maximum dose that did not produce adverse clinical signs was approximately 400 and 500 ng/kg/min, respectively. In the rat, slight ataxia occurred at approximately 490 ng/kg/min and reversed during the infusion period.
Long-term Toxicity Studies
In repeated dose toxicity studies, treprostinil was well tolerated in rats and dogs when given continuously by subcutaneous infusion for up to 6 months or intravenous infusion for up to 3 months. In dogs, dose-limiting toxicity characterized by gastrointestinal changes (emesis, loose stools, intestinal intussusception, hypoactivity, rectal prolapse) contributing to moribundity and death was observed at doses of ≥300 ng/kg/min. This spectrum of gastrointestinal changes has not been observed in the clinical studies.
In both rats and dogs given treprostinil doses up to 450 ng/kg/min and 200 ng/kg/min, respectively, treprostinil-related toxicity was limited to reversible, dose-related reactions at the infusion site and included lumps, masses/nodules, swellings, erythema and/or intermittent pain (dogs only). Microscopic evaluation demonstrated these areas to have local inflammation (abscess or cellulitis), edema, fibrosis or hemorrhage. Although these changes were also observed in saline control animals, the higher incidence and greater severity in the vehicle control and treated groups suggested that these reactions were related to pump implantation, catheterization technique, and/or irritability of the vehicle that was enhanced when administered in combination with treprostinil.
In rats given treprostinil in repeated dose toxicity studies, other treatment-related findings have included reversible redness of extremities (due to the vasodilatory pharmacological activity of treprostinil) observed at all doses and minimal, reversible increases in mean white blood cell counts, total bilirubin and splenic weights (no histological correlation) observed at 450 ng/kg/min. In dogs, there were minimal, transient and reversible decreases in body weight and food consumption, and reversible increases in mean white blood cell counts.
Treprostinil diethanolamine did not demonstrate any carcinogenic effects in mouse or rat carcinogenicity studies. Oral administration of treprostinil diethanolamine to Tg.rasH2 mice at 0, 5, 10 and 20 mg/kg/day in males and 0, 3, 7.5 and 15 mg/kg/day in females daily for 26 weeks did not significantly increase the incidence of tumors. The exposures obtained at the highest dose levels used in males and females are about 8- and 17-fold, respectively, the human exposure at the mean dose of
3.4 mg BID. Oral administration of treprostinil diethanolamine to Sprague Dawley rats at 0, 1, 3 and 10 mg/kg/day daily for 104 weeks did not significantly increase the incidence of tumors. The exposures obtained at the highest dose levels used in males and females are about 21- and 29-fold, respectively, the human exposure.
Table 12 Long-term Toxicity Studies - Continuous Subcutaneous (s.c.) or Intravenous (i.v.) Infusion
Species/ Strain | No./Sex/ Group | Dose (ng/kg/min) | Duration/ Route | Findings | |
|---|---|---|---|---|---|
Species/ Strain | No./Sex/ Group | Dose (ng/kg/min) | Duration/ Route | Findings | |
| Rat | 7 | 0*, 0, 17, 67, | 3 days / | Treprostinil was non-irritating and well tolerated up to | |
| S-D | 200 | s.c. | doses of 200 ng/kg/min. | ||
| 85 | 0, 450 | 2 weeks / | Drug-related effect of regenerative anemia with a shift | ||
| 50, 150 | s.c. | to larger, more immature cells in the low- and mid-dose | |||
| groups. An inverse relationship of dose to alteration of | |||||
| RBC parameters. | |||||
| 8 | 50, 150, 450, | 2 weeks / | Reductions in body weight and food consumption during | ||
| 900, 1500 | i.v. | the first week of the study, and motor activity counts | |||
| generally at mid to high doses. Effects on various | |||||
| function observational battery parameters more | |||||
| prevalent at the high dose. Decreased platelets, | |||||
| increased mean platelet volume, red cell distribution | |||||
| width, and reticulocyte count, as well as altered | |||||
| electrolytes (sodium, potassium and chloride) at mid to | |||||
| high doses | |||||
| 10 | 0, 50, 150, | 1 month / | Minor reversible lesions at the infusion site and redness | ||
| 450 | s.c. | of extremities. | |||
| Rat S-D | 54 | 0*, 0, 450 50, 150 | 3 months / s.c. | Reversible skin lesions, edema, inflammation around pump in all groups. Hematological and clinical chemistry changes were affected by frequent surgical intervention for pump replacement. | |
| 15 | 50, 300, 900 | 13 weeks / i.v. | Reduction in platelet count and skin redness at mid and high doses | ||
| 15 | 0*, 0, 50, 150, 450 | 6 months / s.c. | Treprostinil was generally well tolerated. Slight increases in WBC, total bilirubin, and splenic weights (all reversible) at high dose. Reversible redness of extremities. Lesions, lumps, swellings, and/or thickening of the skin around infusion site - all groups and more frequent at high dose. | ||
| Dog, | 1 | 100, 200 with | 4 days / | Decreased appetite and/or diarrhea. Lumps and/or soft | |
| Beagle | various | s.c. | swellings at and around infusion site. | ||
| buffers) | |||||
| 32 | 0, 600 → 400 | 2 weeks / | Vomiting and loose stools. Lesions and/or hemorrhage | ||
| 50, 200 | s.c. | and congestion at infusion site. Two high-dose males | |||
| had intestinal intussusceptions with one having rectal | |||||
| prolapse. | |||||
| 2 | 50, 100, 200, | 2 weeks | Soft and/or liquid feces and reductions in body weight | ||
| 400 | i.v. | gain were seen at all doses, but were most severe at | |||
| 24 high dose. Reductions in food consumption at mid | |||||
| dose. Effect on platelets and mean platelet volume at | |||||
| higher doses, and jejunal hemorrhage in one high dose | |||||
| animal and associated gross changes in the GI tract of | |||||
| other animals were all considered to be treatment- | |||||
| related | |||||
| 4 | 50, 100, 200 | 13 weeks / | Soft or liquid feces, red skin on the pinnae, muzzle or | ||
| i.v. | lower jaw at the mid and high-dose, reduced body | ||||
| weight and food consumption in high-dose animals, and | |||||
| elevated mean platelet volume in high dose males and | |||||
| mid and high dose females, all of which were reversible | |||||
| following a 4-week recovery period. | |||||
| 3 | 0*, 0, 50, 150 → 100, 300 → 200 | 13 weeks / s.c. | Reversible dose-related increase in WBC. Redness of skin and at infusion site. Occasional pain when infusion site palpated. | ||
| Dark discoloration, masses and/or thickening at and | |||||
| around infusion site, with histological correlation of | |||||
| edema, hemorrhage, fibrosis, and cellulitis in all groups, | |||||
| with less incidence and/or severity in saline control. | |||||
| 4 | 0*, 0, 50, | 6 months / | Redness of skin. Occasional pain when infusion site | ||
| 100, 200 | s.c. | palpated. Reversible lumps and/or swellings at/around | |||
| infusion site with histological findings consisting of | |||||
| cellulitis, edema, fibrosis, and hemorrhage in all groups, | |||||
| with less incidence and/or severity in saline group. | |||||
S-D, Sprague-Dawley *Saline.
Reproductive and Developmental Toxicology: Treprostinil had no effect on adult reproduction, conceptus, early development and growth in rats given up to 450 ng/kg/min by continuous subcutaneous infusion. Administration of treprostinil by continuous subcutaneous infusion during major organogenesis was not teratogenic in pregnant rats at doses up to 900 ng/kg/min (Table 13).
In pregnant rabbits, developmental toxicity characterized by minimal increases in fetal skeletal variations/litter was observed at doses of 150 and 300 ng/kg/min and was associated with maternal toxicity. No developmental toxicity was seen in rabbits at 50 ng/kg/min.
In the Pre- and Postnatal Developmental Study in rats given treprostinil by continuous subcutaneous infusion at doses of 50, 150 or 450 ng/kg/min, the F1 mating index was reduced (not statistically significant) at 450 ng/kg/min. There were no other treatment-related changes in this study and the no observable adverse effect level (NOAEL) for F0 maternal toxicity was 450 ng/kg/min, the conservative NOAEL for F1 male and female reproductive toxicity was 150 ng/kg/min, and the NOAEL for F0 reproductive toxicity and for F1 and F2 developmental toxicity was 450 ng/kg/min.
Table 13 Reproduction and Teratology Studies - Continuous Subcutaneous Infusion
| Study | Species/ Strain | No./ Group | Dose (ng/kg/min) | Duration | Findings |
|---|---|---|---|---|---|
| Study | Species/ Strain | No./ Group | Dose (ng/kg/min) | Duration | Findings |
| Segment I Fertility and General Reproductive Performance | Rat Sprague-Dawley | 25 M 25 F | 0, 50, 150, 450 | M: 10 weeks (pre-breed) and 2 weeks (mating). F: 2 weeks (pre-breed), 2 weeks (mating) and continued until GD Day 6 | NOAEL was 50 ng/kg/min for both adult male and female systemic toxicity, and ≥450 ng/kg/min for reproductive and developmental toxicity. |
| Segment II Teratology | Rat Sprague- Dawley | 25 F mated | 0, 50, 150, 450, 900 | GD 6-20 | NOAEL was 150 and ≥900 ng/kg/min for maternal and developmental toxicity, respectively. |
Rabbit New Zealand White | 20 F mated | 0, 50, 150, 300 | GD 6-19 | No NOAEL was established for maternal toxicity; and was 50 ng/kg/min for developmental toxicity. | |
| Segment III Peri-postnatal | Rat Sprague-Dawley | 25 F mated | 0, 50, 150, 450 | GD 6-21 | NOAEL was 450 ng/kg/min for F0 maternal toxicity; 150 ng/kg/min for F1 offspring; and 450 ng/kg/min for F0 reproductive F1 and F2 developmental toxicity. |
GD, Gestational Day
Genotoxicity
Treprostinil is not mutagenic or clastogenic in in vitro and in vivo genetic toxicological assays (Table 14).
Table 14 In Vivo and In Vitro Mutagenicity Studies
| Study | Species | Dose/ Concentration | Findings |
|---|---|---|---|
| Ames Assay | Salmonella typhimurium | Up to 5000 µg/plate with and without S9 metabolic activation | Treprostinil was non-mutagenic at concentrations ≤500 µg/plate. (Above these concentrations, toxicity of treprostinil toward the bacterial tester strains precluded further Evaluation of the results.) |
| Bacterial Reverse Mutation Assay | Salmonella typhimurium E. coli WP2 uvrA | Up to 5000 µg/plate with and without S9 metabolic activation | Treprostinil was non-mutagenic at concentrations ≤5000 µg/plate. |
Mouse Lymphoma Forward Mutation Assay | Mouse lymphoma L5178Y cell line | 300 and 400 µg/mL with and without S9 metabolic activation | Treprostinil was negative for inducing forward mutations over a range of concentrations. |
| Micronucleus Test | Rats Sprague- Dawley | 0, 500, 1000, 1500 ng/kg/min | Treprostinil was negative in this test. |
17. Supporting Product Monographs
PrREMODULIN® treprostinil injection, 1, 2.5, 5, and 10 mg/mL of treprostinil, Control Number: 302563, product monograph, United Therapeutics Corp. (21-04-2026)