


Product Monograph - Codeine Contin 200mg Controlled Release Tab
Recent Major Label Changes
| 7 Warnings and Precautions, Dependence, Tolerance and/or Abuse Liability, Addiction Abuse and Misuse | 03/2025 |
|---|---|
| 7 Warnings and Precautions, Neurologic, Interactions with CNS Depressants (including benzodiazepines and alcohol) | 03/2025 |
| 7 Warnings and Precautions, Neurologic, Opioid Induced Hyperalgesia | 032025 |
Table of Contents
Certain sections or subsections that are not applicable at the time of the preparation of the most recent authorized product monograph are not listed.
Recent Major Label Changes ....................................................................................... 2
Table of Contents .......................................................................................................... 2
Part I: Healthcare Professional Information ................................................................ 4
1 Indications ........................................................................................................... 4
1.1 Pediatrics ................................................................................................... 4
1.2 Geriatrics ................................................................................................... 4
2 Contraindications ............................................................................................... 4
3 Serious Warnings and Precautions Box .......................................................... 5
4 Dosage and Administration ............................................................................... 6
4.1 Dosing Considerations ............................................................................... 6
4.2 Recommended Dose and Dosage Adjustment .......................................... 7
4.4 Administration .......................................................................................... 10
4.5 Missed Dose ............................................................................................ 10
5 Overdose ........................................................................................................... 10
6 Dosage Forms, Strengths, Composition, and Packaging ............................. 11
7 Warnings and Precautions .............................................................................. 12
General ............................................................................................................... 12
Carcinogenesis and Genotoxicity ....................................................................... 12
Dependence, Tolerance and/or Abuse Liability .................................................. 12
Endocrine and Metabolism ................................................................................. 14
Gastrointestinal ................................................................................................... 15
Neurologic .......................................................................................................... 15
Perioperative Considerations.............................................................................. 16
Renal .................................................................................................................. 17
Reproductive Health ........................................................................................... 17
Respiratory ......................................................................................................... 17
7.1 Special Populations ................................................................................. 18
7.1.1 Pregnancy ............................................................................................ 18
7.1.2 Breastfeeding ....................................................................................... 19
7.1.3 Pediatrics ............................................................................................. 19
7.1.4 Geriatrics .............................................................................................. 20
8 Adverse Reactions ........................................................................................... 20
8.1 Adverse Reaction Overview ..................................................................... 20
8.3 Less Common Clinical Trial Adverse Reactions ...................................... 21
8.5 Post-Market Adverse Reactions .............................................................. 22
9 Drug Interactions .............................................................................................. 22
9.1 Serious Drug Interactions ........................................................................ 22
9.2 Drug Interactions Overview ...................................................................... 23
9.3 Drug-Behaviour Interactions .................................................................... 23
9.4 Drug-Drug Interactions ............................................................................. 23
9.5 Drug-Food Interactions ............................................................................ 25
9.6 Drug-Herb Interactions ............................................................................. 25
9.7 Drug-Laboratory Test Interactions ........................................................... 26
10 Clinical Pharmacology ..................................................................................... 26
10.1 Mechanism of Action ............................................................................... 26
10.2 Pharmacodynamics ................................................................................. 26
10.3 Pharmacokinetics .................................................................................... 27
11 Storage, Stability, and Disposal ...................................................................... 29
12 Special Handling Instructions ......................................................................... 29
Part 2: Scientific Information ..................................................................................... 30
13 Pharmaceutical Information ............................................................................ 30
14 Clinical Trials .................................................................................................... 31
16 Non-Clinical Toxicology ................................................................................... 31
Patient Medication Information .................................................................................. 32
Part I: Healthcare Professional Information
1 Indications
CODEINE CONTIN (codeine controlled release tablets) is indicated for the relief of mild to moderate pain in adults requiring the prolonged use of an opioid analgesic preparation.
CODEINE CONTIN is not indicated as an as-needed (prn) analgesic.
1.1 Pediatrics
Pediatrics (<18 years of age):
Regardless of the clinical setting, codeine, including CODEINE CONTIN, should not be used in children below the age of 12 years because of the risk of opioid toxicity due to the variable and unpredictable metabolism of codeine to morphine (see 2 Contraindications; 4 Dosage and Administration; 7.1.3 Pediatrics; 10.3 Pharmacokinetics, Special Populations and Conditions, Pediatrics)
CODEINE CONTIN has not been studied in the pediatric population, therefore the use of CODEINE CONTIN is not recommended in patients over 12 and under 18 years of age (see 2 Contraindications).
1.2 Geriatrics
Geriatrics (>65 years of age): Evidence from clinical studies and experience suggests that use in the geriatric population is associated with differences in safety or effectiveness. (see 7.1.4 Geriatrics; 10.3 Pharmacokinetics, Special Populations and Conditions, Geriatrics). In general, dose selection for an elderly patient should be cautious, usually starting at the low end of the dosing range, and titrated slowly, reflecting the greater frequency of decreased hepatic, renal, or cardiac function, concomitant disease or other drug therapy (see 4.2 Recommended Dose and Dose Adjustment).
2 Contraindications
CODEINE CONTIN is contraindicated in:
- Patients who are hypersensitive to this drug or to any ingredient in the formulation, including any non-medicinal ingredient, or component of the container. For a complete listing, see 6 Dosage Forms, Strengths, Composition and Packaging.
- Patients with known or suspected mechanical gastrointestinal obstruction (e.g., bowel obstruction, strictures) or any diseases/conditions that affect bowel transit (e.g., ileus of any type).
- Patients with suspected surgical abdomen (e.g., acute appendicitis or pancreatitis).
- Patients with intermittent or short duration pain that can be managed with other pain medications.
- Patients with acute or mild pain that can be managed with immediate release pain medications.
- Patients with acute or severe bronchial asthma, chronic obstructive airway, and status asthmaticus.
- Patients with acute respiratory depression, elevated carbon dioxide (CO2) levels in the blood, and cor pulmonale.
- Patients with acute alcoholism, delirium tremens, and convulsive disorders.
- Patients with severe CNS depression, increased cerebrospinal or intracranial pressure, and head injury.
- CYP2D6 ultra-rapid metabolizers who convert codeine into its active metabolite more rapidly and completely than other people (see 5 Overdose; 7 Warnings and Precautions, Endocrine and Metabolism, Risk of Death in Ultra-Rapid Metabolizers of Codeine)
- Patients taking Monoamine Oxidase Inhibitors (MAOIs) or within 14 days of such therapy.
- Women who are breast-feeding, pregnant, or during labour and delivery (see 3 Serious Warnings and Precautions Box; 7.1.1 Pregnancy; 7.1.2 Breastfeeding).
- Pediatric patients (<18 years of age) who have undergone tonsillectomy and/or adenoidectomy for obstructive sleep apnoea syndrome.
3 Serious Warnings and Precautions Box
Because of the risks of addiction, abuse, and misuse with opioids, even at recommended doses, and because of the risks of overdose and death with controlled-release opioid formulations, CODEINE CONTIN should only be used in patients for whom alternative treatment options (e.g., non-opioid analgesics) are ineffective, not tolerated, or would be otherwise inadequate to provide appropriate management of pain (see 4.1 Dosing Considerations).
CODEINE CONTIN poses risks of opioid addiction, abuse, and misuse, which can lead to overdose and death. Each patient’s risk should be assessed prior to prescribing CODEINE CONTIN, and all patients should be monitored regularly for the development of these behaviours or conditions (see 7 Warnings and Precautions, Dependence, Tolerance and/or Abuse Liability, Addiction, Abuse and Misuse). CODEINE CONTIN should be stored securely to avoid theft or misuse.
Serious, life-threatening, or fatal respiratory depression may occur with use of CODEINE CONTIN. Infants exposed in-utero or through breast milk are at risk of life-threatening respiratory depression upon delivery or when nursed. Patients should be monitored for respiratory depression, especially during initiation of Codeine Contin or following a dose increase. CODEINE CONTIN must be swallowed whole; cutting, breaking, crushing, chewing, or dissolving CODEINE CONTIN can lead to dangerous adverse events including death (see 7 Warnings and Precautions, General). Further, instruct patients of the hazards related to taking opioids including fatal overdose. |
|---|
Accidental ingestion of even one dose of CODEINE CONTIN, especially by children, can result in a fatal overdose of codeine (see 11 Storage, Stability and Disposal, for instructions on proper disposal).
Prolonged maternal use of CODEINE CONTIN during pregnancy can result in neonatal opioid withdrawal syndrome, which may be life-threatening (see 7 Warnings and Precautions, Dependence, Tolerance, and/or Abuse Liability, Neonatal Opioid Withdrawal Syndrome (NOWS).
The co-ingestion of alcohol with CODEINE CONTIN should be avoided as it may result in dangerous additive effects, causing serious injury or death (see 7 Warnings and Precautions, Neurologic, Interactions with Central Nervous System Depressants (Including Benzodiazepines and Alcohol) and 9.4. Drug-Drug Interactions).
Concomitant use of opioids with benzodiazepines or other CNS depressants, including alcohol, may result in profound sedation, respiratory depression, coma, and death (see 7 Warnings and Precautions, Neurologic, Interactions with Central Nervous System Depressants (Including Benzodiazepines and Alcohol) and 9.4 Drug-Drug Interactions).
|
|---|
4 Dosage and Administration
4.1 Dosing Considerations
- All doses of opioids carry an inherent risk of fatal or non-fatal adverse events. This risk is increased with higher doses. For the management of chronic non-cancer, non-palliative pain, it is recommended that 600 mg (90 morphine milligram equivalent) daily of CODEINE CONTIN not be exceeded. Each patient should be assessed for their risk prior to prescribing CODEINE CONTIN, as the likelihood of experiencing serious adverse events can depend upon the type of opioid, duration of treatment, level of pain as well as the patient’s own level of tolerance. In addition, the level of pain should be assessed routinely to confirm the most appropriate dose and the need for further use of CODEINE CONTIN (see 4.2 Recommended Dose and Dosage Adjustment, Adjustment or Reduction of Dosage).
- CODEINE CONTIN should only be used in patients for whom alternative treatment options are ineffective or not tolerated (e.g., non-opioid analgesics).
- CODEINE CONTIN should be used with caution within 12 hours pre-operatively but should not be used in the early post-operative period (12 to 24 hours post-surgery) unless the patient is ambulatory and gastrointestinal function is normal (see 7 Warnings and Precautions, Peri-operative Considerations).
- Pediatrics: Regardless of clinical setting, codeine (including CODEINE CONTIN) should not be used in children below the age of 12 years because of the risk of opioid toxicity due to the variable and unpredictable metabolism of codeine to morphine. CODEINE CONTIN should not be used in individuals less than 18 years old.
4.2 Recommended Dose and Dosage Adjustment
Adults
Individual dosing requirements vary considerably based on each patient's age, weight, severity and cause of pain, and medical and analgesic history.
Doses of CODEINE CONTIN are expressed as codeine base. Codeine phosphate formulations contain approximately 75% codeine base. Patients currently receiving oral immediate release formulations of plain codeine phosphate may be transferred to CODEINE CONTIN at an approximately 25% lower total daily codeine dosage, equally divided into two 12 hourly CODEINE CONTIN doses.
- Patients Not Receiving Opioids at the Time of Initiation of Codeine Treatment: Patients with pain who are not currently receiving other opioid analgesics, or who are receiving fewer than four tablets per day of a codeine combination preparation, should be initiated at a dose of CODEINE CONTIN 50 mg every 12 hours and the dose titrated as needed.
- Patients Currently Receiving Opioids: For patients who are currently receiving analgesic combinations of codeine phosphate and acetaminophen or acetylsalicylic acid (ASA), Table 1 provides a guide to the recommended initial and maintenance doses of CODEINE CONTIN.
Table 1 – Conversion from Acetaminophen (or ASA) plus Codeine Phosphate Combinations
| Number of 30 mg Codeine Combination Tablets per Day | Initial Dose of CODEINE CONTIN | Maintenance Dose of CODEINE CONTIN |
| 4 – 6 | 50 mg q12h | 100 mg q12h |
| 7 – 9 | 100 mg q12h | 150 mg q12h |
| 10 – 12 | 150 mg q12h | 200 mg q12h |
| >12 | 200 mg q12h | as needed (maximum 300 mg q12h) |
For patients who are receiving an alternate opioid, the "oral codeine phosphate equivalent" of the analgesic presently being used should be determined. Having determined the total daily dosage of the present analgesic, Table 2 can be used to calculate the approximate daily oral codeine phosphate dosage that should provide equivalent analgesia. An approximately 25% lower dose of CODEINE CONTIN should then be prescribed, to account for the change from codeine phosphate to codeine base. This dose should be equally divided into two 12 hourly doses. Further dose reductions should also be considered due to incomplete cross-tolerance between opioids.
Opioid Rotation: Conversion ratios for opioids are subject to variations in kinetics governed by genetics and other factors. When switching from one opioid to another, consider reducing the calculated dose by 25-50% to minimize the risk of overdose. Subsequently, up-titrate the dose, as required, to reach the appropriate maintenance dose.
Table 2 – Opioid Conversion Tablea
| Opioids | To convert to oral morphine equivalent | To convert from oral morphine multiply by | Daily 90 mg MEDb |
| Morphine | 1 | 1 | 90 mg |
| Codeine | 0.15 | 6.67 | 600 mg |
| Hydromorphone | 5 | 0.2 | 18 mg |
| Oxycodone | 1.5 | 0.667 | 60 mg |
| Tapentadol | 0.3-0.4 | 2.5-3.33 | 300 mg |
| Tramadol | 0.1-0.2 | 6 | *** |
| Methadone | Morphine dose equivalence is not reliably established | ||
*** The maximum recommended daily dose of tramadol is 300 mg – 400 mg depending on the formulation.
- a. Adapted from the 2017 Canadian guideline for opioids for chronic non-cancer pain. McMaster University; 2017
- b. MED. Morphine Equivalent Dose
- • Patients with Hepatic Impairment: Start these patients cautiously with lower doses of CODEINE CONTIN or with longer dosing intervals and titrate slowly while carefully monitoring for side effects. Dosage reduction is recommended in severe hepatic impairment due to the risk of toxicity (see 10.3 Pharmacokinetics, Special Populations and Conditions, Hepatic Insufficiency).
- •
Patients with Renal Impairment: Dosage reduction is recommended in severe renal impairment due to the risk of toxicity (see 10.3 Pharmacokinetics, Special Populations and Conditions, Renal Insufficiency).
Clearance may be decreased, and the metabolites may accumulate to much higher plasma levels in patients with renal failure as compared to patients with normal renal function. Start these patients cautiously with lower doses of CODEINE CONTIN or with longer dosing intervals and titrate slowly while carefully monitoring for side effects.
- • Use with Non-Opioid Medications: If a non-opioid analgesic is being provided, it may be continued. If the non-opioid is discontinued, consideration should be given to increasing the opioid dose to compensate for the non-opioid analgesic. CODEINE CONTIN can be safely used concomitantly with usual doses of other non-opioid analgesics.
- •
Dose Titration: Dose titration is the key to success with opioid analgesic therapy. Proper optimization of doses scaled to the relief of the patient's pain should aim at regular administration of the lowest dose of CODEINE CONTIN which will achieve the overall treatment goal of satisfactory pain relief with acceptable side effects.
Dosage adjustments should be based on the patient's clinical response. In patients receiving CODEINE CONTIN chronically, the dose should be titrated at intervals of 48 hours to that which provides satisfactory pain relief without unmanageable side effects. Doses of CODEINE CONTIN above 300 mg q12h have not been extensively studied, and above these levels it is preferable that patients be transferred to an opioid such as morphine, which is recommended for severe pain. CODEINE CONTIN is designed to allow 12 hourly dosing.
If pain repeatedly occurs at the end of the dosing interval it is generally an indication for a dosage increase rather than more frequent administration of controlled release codeine (CODEINE CONTIN).
- • Adjustment or Reduction of Dosage: Physical dependence with or without psychological dependence tends to occur with chronic administration of opioids, including CODEINE CONTIN. Withdrawal (abstinence) symptoms may occur following abrupt discontinuation of therapy. These symptoms may include body aches, diarrhea, gooseflesh, loss of appetite, nausea, nervousness or restlessness, runny nose, sneezing, tremors or shivering, stomach cramps, tachycardia, trouble with sleeping, unusual increase in sweating, palpitations, unexplained fever, weakness and yawning.
- •
Following successful relief of pain, periodic attempts to reduce the opioid dose should be made. Smaller doses or complete discontinuation may become feasible due to a change in the patient's condition or mental state.
Patients on prolonged therapy should be withdrawn gradually from the drug if it is no longer required for pain control. In patients who are appropriately treated with opioid analgesics and who undergo gradual withdrawal for the drug, these symptoms are usually mild (see 7 Warnings and Precautions). Tapering should be individualized and carried out under medical supervision.
Patients should be informed that reducing and/or discontinuing opioids decreases their tolerance to these drugs. If treatment needs to be re-initiated, the patient must start at the lowest dose and titrate up to avoid overdose.
Opioid analgesics may only be partially effective in relieving dysesthetic pain, postherpetic neuralgia, stabbing pains, activity-related pain and some forms of headache. That is not to say that patients suffering from some of these forms of chronic pain should not be given an adequate trial of opioid analgesics, but it may be necessary to refer such patients at an early time to other forms of pain therapy.
- •
Management of Patients Requiring Rescue Medication: For patients whose dose has been titrated to the recommended maintenance dose, without attainment of adequate analgesia, the total daily dose may be increased, unless precluded by side effects. If episodes of pain are encountered with appropriate adjustments of the CODEINE CONTIN dose, plain acetaminophen may be given (325-650 mg q4-6h p.r.n. to a maximum of 4,000 mg/24 hours). Fentanyl products should not be used as rescue medication in patients taking CODEINE CONTIN. If immediate release codeine phosphate preparations or acetaminophen plus codeine phosphate combination analgesics (q4-6h p.r.n.) are used for pain, the doses of codeine phosphate* are 15, 30, 45, 60, 90 mg for patients receiving CODEINE CONTIN 100, 200, 300, 400, 600 mg/day, respectively.
(*based on a rescue medication dose of codeine base which should not exceed 1/8 of the daily dose of CODEINE CONTIN.)
Pediatrics (<18 years of age)
Health Canada has not authorized an indication for pediatric use (see 4.1 Dosing Considerations; 7.1.3 Pediatrics).
Geriatrics (>65 years of age)
Respiratory depression has occurred in the elderly following administration of large initial doses of opioids to patients who were not opioid-tolerant or when opioids were co-administered with other agents that can depress respiration. CODEINE CONTIN should be initiated at a low dose and slowly titrated to effect (see 7.1.4 Geriatrics; 10.3 Pharmacokinetics, Special Populations and Conditions, Geriatrics).
4.4 Administration
CODEINE CONTIN must be swallowed whole and should not be chewed, dissolved or crushed. Taking broken, chewed, dissolved or crushed tablets could lead to rapid release and absorption of a potentially fatal dose of codeine (see 7 Warnings and Precautions, General).
All strengths may be halved, except 50 mg. The half tablets must also be swallowed intact, they should not be chewed, dissolved or crushed.
CODEINE CONTIN may be taken with or without food with a glass of water.
CODEINE CONTIN is not indicated for rectal administration.
4.5 Missed Dose
If the patient forgets to take one or more doses, they should take their next dose at the next scheduled time and in the normal amount.
5 Overdose
Signs and Symptoms
Serious overdosage with opioids may be characterized by respiratory depression (a decrease in respiratory rate and/or tidal volume, Cheyne-Stokes respiration, cyanosis), dizziness, confusion, extreme somnolence progressing to stupor or coma, miosis, hypotonia, cold and clammy skin, toxic leukoencephalopathy (TLE), delayed post-hypoxic leukoencephalopathy (DPHL) and sometimes bradycardia, hypotension and hypoglycemia. Severe overdose may result in apnea, circulatory collapse, cardiac arrest and death.
Treatment
Primary attention should be given to the establishment of adequate respiratory exchange through the provision of a patent airway and controlled or assisted ventilation. The opioid antagonist naloxone hydrochloride is a specific antidote against respiratory depression due to overdosage or as a result of unusual sensitivity to opioids. An appropriate dose of the antagonist should therefore be administered, preferably by the intravenous route. The usual initial i.v. adult dose of naloxone is 0.4 mg or higher. Concomitant efforts at respiratory resuscitation should be carried out. Since the duration of action of opioids, particularly sustained release formulations, may exceed that of the antagonist, the patient should be under continued surveillance and doses of the antagonist should be repeated as needed to maintain adequate respiration.
An antagonist should not be administered in the absence of clinically significant respiratory or cardiovascular depression. Oxygen, intravenous fluids, vasopressors and other supportive measures should be used as indicated.
In individuals physically dependent on opioids, the administration of the usual dose of opioid antagonist will precipitate an acute withdrawal syndrome. The severity of this syndrome will depend on the degree of physical dependence and the dose of antagonist administered. The use of opioid antagonists in such individuals should be avoided if possible. If an opioid antagonist must be used to treat serious respiratory depression in the physically dependent patient, the antagonist should be administered with extreme care by using dosage titration, commencing with 10 to 20% of the usual recommended initial dose.
Evacuation of gastric contents may be useful in removing unabsorbed drug, particularly when a sustained release formulation has been taken.
| For the most recent information in the management of a suspected drug overdose, contact your regional poison control centre or Health Canada’s toll-free number 1-844-POISON-X (1-844-764-7669). |
|---|
6 Dosage Forms, Strengths, Composition, and Packaging
Table 3 – Dosage Forms, Strengths, and Composition
Description and Composition
Each CODEINE CONTIN 50 mg tablet contains 26.5 mg of codeine monohydrate and 31.35 mg of codeine sulfate trihydrate (each equivalent to 25 mg codeine anhydrous). CODEINE CONTIN 50 mg tablets are blue, round, film-coated with PF imprinted on one side and CC 50 on the other side.
Each CODEINE CONTIN 100 mg tablet contains 53 mg of codeine monohydrate and 62.7 mg of codeine sulfate trihydrate (each equivalent to 50 mg codeine anhydrous). CODEINE CONTIN 100 mg tablets are yellow, round, scored film-coated with PF imprinted on one side and CC 100 on the other side.
Each CODEINE CONTIN 150 mg tablet contains 79.5 mg of codeine monohydrate and 94.1 mg of codeine sulfate trihydrate (each equivalent to 75 mg codeine anhydrous). CODEINE CONTIN 150 mg tablets are red, round, scored film-coated with PF imprinted on one side and CC 150 on the other side.
Each CODEINE CONTIN 200 mg tablet contains 106 mg of codeine monohydrate and 125.4 mg of codeine sulfate trihydrate (each equivalent to 100 mg codeine anhydrous). CODEINE CONTIN 200 mg tablets are orange, caplet shaped, scored film-coated with PF imprinted on one side and CC 200 on the other side.
| Route of Administration | Dosage Form / Strength | Non-medicinal Ingredients |
| Oral | Controlled Release Tablets / 50 mg, 100 mg 150 mg and 200 mg | Hydroxyethyl cellulose, hydroxypropyl cellulose, hydroxypropyl methylcellulose, lactose, magnesium stearate, polyethylene glycol, stearyl alcohol, talc and titanium dioxide In addition, the tablet strengths listed below contain the following dyes: 50 mg - FD&C Blue No. 2 Aluminum Lake 100 mg - D&C Yellow No. 10 Aluminum Lake, FD&C Yellow No. 6 Aluminum Lake 150 mg - FD&C Yellow No. 6 Aluminum Lake, FD&C Red No. 40 Aluminum Lake 200 mg - FD&C Yellow No. 6 Aluminum Lake |
Packaging
CODEINE CONTIN is supplied in opaque, plastic bottles containing 50 or 60 tablets.
7 Warnings and Precautions
See 3 Serious Warnings and Precautions Box
General
CODEINE CONTIN must be swallowed whole, and should not be chewed, dissolved or crushed. Taking broken, chewed, dissolved or crushed tablets could lead to the rapid release and absorption of a potentially fatal dose of codeine. All strengths may be halved, except 50 mg. The half tablets must also be swallowed intact, they should not be chewed, dissolved or crushed.
Patients should be instructed not to give CODEINE CONTIN to anyone other than the patient for whom it was prescribed, as such, inappropriate use may have severe medical consequences, including death. CODEINE CONTIN should be stored securely to avoid theft or misuse.
CODEINE CONTIN should only be prescribed by healthcare professionals who are knowledgeable in the continuous administration of potent opioids, in the management of patients receiving potent opioids for the treatment of pain, and in the detection and management of respiratory depression, including the use of opioid antagonists.
Patients should be cautioned not to consume alcohol while taking CODEINE CONTIN, as it may increase the chance of experiencing dangerous side effects, including death.
Patients should be counselled to discontinue codeine products and to seek urgent medical help at the earliest sign of codeine toxicity including symptoms such as confusion, shallow breathing, or extreme sleepiness which may be life threatening.
Carcinogenesis and Genotoxicity
No carcinogenesis and genotoxicity data are available in humans. (See 16 Non-clinical Toxicology).
Cardiovascular
Codeine administration may result in severe hypotension in patients whose ability to maintain adequate blood pressure is compromised by reduced blood volume, or concurrent administration of such drugs as phenothiazines and other tranquilizers, sedative/hypnotics, tricyclic antidepressants or general anesthetics. These patients should be monitored for signs of hypotension after initiating or titrating the dose of CODEINE CONTIN.
The use of CODEINE CONTIN in patients with circulatory shock should be avoided as it may cause vasodilation that can further reduce cardiac output and blood pressure.
Dependence, Tolerance and/or Abuse Liability
As with other opioids, tolerance and physical dependence may develop upon repeated administration of CODEINE CONTIN and there is potential for development of psychological dependence. CODEINE CONTIN should therefore be prescribed and handled with the degree of caution appropriate to the use of a drug with abuse potential.
Physical dependence and tolerance reflect the neuroadaptation of the opioid receptors to chronic exposure to an opioid and are separate and distinct from abuse and addiction. Tolerance, as well as physical dependence, may develop upon repeated administration of opioids, and are not by themselves evidence of an addictive disorder or abuse.
In addition, abuse of opioids can occur in the absence of true addiction and is characterized by misuse for non-medical purposes.
Addiction, Abuse and Misuse: Like all opioids, CODEINE CONTIN is a potential drug of abuse and misuse, which can lead to overdose and death. Therefore, CODEINE CONTIN should be prescribed and handled with caution.
Patients should be assessed for their clinical risks for opioid abuse or addiction prior to being prescribed opioids. All patients receiving opioids should be routinely monitored for signs of misuse and abuse.
Opioids, such as CODEINE CONTIN, should be used with particular care in patients with a history of alcohol and illicit/prescription drug abuse and other mental health disorders including, but not limited to major depression and anxiety. However, concerns about abuse, addiction, and diversion should not prevent the proper management of pain.
CODEINE CONTIN tablets are intended for oral use only. The tablets should be swallowed whole, and not chewed or crushed. With parenteral abuse, the tablet excipients can be expected to result in local tissue necrosis, infection, pulmonary granulomas, and increased risk of endocarditis and valvular heart injury, which may also be fatal. Abuse of oral dosage forms can be expected to result in serious adverse events, including death.
Efforts should be made to promote appropriate opioid prescribing practices that balance the uncertainties between the benefits and risks of opioid medications based on the individual needs of each patient.
Withdrawal Symptoms: Patients on prolonged therapy should be tapered gradually from the drug if it is no longer required for pain control. Withdrawal symptoms may occur following abrupt discontinuation of therapy or upon administration of an opioid antagonist. Some of the symptoms that may be associated with abrupt withdrawal of an opioid analgesic include body aches, diarrhea, gooseflesh, loss of appetite, nausea, nervousness or restlessness, anxiety, runny nose, sneezing, tremors or shivering, stomach cramps, tachycardia, trouble with sleeping, unusual increase in sweating, palpitations, unexplained fever, weakness and yawning (see 8 Adverse Reactions; 4.2 Recommended Dose and Dosage Adjustment, Adjustment or Reduction of Dosage).
Neonatal Opioid Withdrawal Syndrome (NOWS): Prolonged maternal use of opioid during pregnancy can result in withdrawal signs in the neonate. Neonatal opioid withdrawal syndrome, unlike opioid withdrawal syndrome in adults, may be life-threatening.
Neonatal opioid withdrawal syndrome presents as irritability, hyperactivity and abnormal sleep pattern, high pitched cry, tremor, vomiting, diarrhea and failure to gain weight. The onset, duration, and severity of neonatal opioid withdrawal syndrome vary based on the specific opioid used, duration of use, timing and amount of last maternal use, and rate of elimination of the drug by the newborn.
Use of CODEINE CONTIN is contraindicated in pregnant women (see 2 Contraindications).
Use in Drugs and Alcohol Addiction: CODEINE CONTIN is an opioid with no approved use in the management of addictive disorders. Its proper usage in individuals with drug or alcohol dependence, either active or in remission is for the management of pain requiring opioid analgesia.
Patients with a history of addiction to drugs or alcohol may be at higher risk of becoming addicted to CODEINE CONTIN unless used under extreme caution and awareness.
In Vitro Dissolution of Interaction with Alcohol: Increasing concentrations of alcohol in the dissolution medium resulted in a slight decrease in the rate of release of codeine from CODEINE CONTIN tablets.
Driving and Operating Machinery
CODEINE CONTIN may impair the mental and/or physical abilities needed for certain potentially hazardous activities such as driving a car or operating machinery. Patients should be cautioned accordingly. Patients should also be cautioned about the combined effects of codeine with other CNS depressants, including other opioids, phenothiazine, sedative/hypnotics and alcohol.
Endocrine and Metabolism
Adrenal Insufficiency: Cases of adrenal insufficiency have been reported with opioid use, more often following greater than one month of use. Presentation of adrenal insufficiency may include non-specific symptoms and signs including nausea, vomiting, anorexia, fatigue, weakness, dizziness, and low blood pressure. If adrenal insufficiency is suspected, confirm the diagnosis with diagnostic testing as soon as possible. If adrenal insufficiency is diagnosed, treat with physiologic replacement doses of corticosteroids. Wean the patient off of the opioid to allow adrenal function to recover and continue corticosteroid treatment until adrenal function recovers. Other opioids may be tried as some cases reported use of a different opioid without recurrence of adrenal insufficiency. The information available does not identify any particular opioids as being more likely to be associated with adrenal insufficiency.
Risk of Death in Ultra-Rapid Metabolizers of Codeine: Some individuals may be ultra-rapid metabolizers due to a specific CYP2D6*2x2 genotype. These individuals convert codeine into its active metabolite, morphine, more rapidly and completely than other people. This rapid conversion results in higher than expected serum morphine levels. Even at labelled dosage regimens, individuals who are ultra-rapid metabolizers may experience overdose symptoms such as extreme sleepiness, confusion, or shallow breathing (see 7.1.2 Breast-feeding).
The prevalence of this CYP2D6 phenotype varies widely and has been estimated at 0.5 to 1% in Chinese and Japanese, 0.5 to 1% in Hispanics, 1 to 10% in Caucasians, 3% in African Americans, and 16 to 28% in North Africans, Ethiopians, and Arabs. Data are not available for other ethnic groups. When physicians prescribe codeine-containing drugs, they should choose the lowest effective dose for the shortest period of time and inform their patients about these risks and the signs of morphine overdose (see 4.1 Dosing Considerations).
Gastrointestinal
Codeine and other morphine-like opioids have been shown to decrease bowel motility. Codeine may obscure the diagnosis or clinical course of patients with acute abdominal conditions (see 2 Contraindications; 8.1 Adverse Reaction Overview, Nausea and Vomiting and Constipation).
Hepatic/Biliary/Pancreatic
No formal studies have been conducted in patients with hepatic impairment so the pharmacokinetics of codeine in this patient population are unknown. Start these patients cautiously with lower doses of CODEINE CONTIN or with longer dosing intervals and titrate slowly while carefully monitoring for side effects. Dosage reduction is recommended in severe hepatic impairment due to the risk of toxicity.
Neurologic
Interactions with CNS Depressants (including benzodiazepines and alcohol): Codeine should be used with caution and in reduced dosage during concomitant administration of other opioid analgesics, general anesthetics, phenothiazines and other tranquilizers, sedative, -hypnotics, tricyclic antidepressants, antipsychotics, antihistamines, benzodiazepines, gabapentinoids, baclofen, centrally-active anti-emetics and other CNS depressants. Respiratory depression, hypotension and profound sedation, coma or death may result.
Observational studies have demonstrated that concomitant use of opioid analgesics and benzodiazepines increases the risk of drug-related mortality compared to use of opioid analgesics alone. Because of similar pharmacological properties, it is reasonable to expect similar risk with the concomitant use of other CNS depressant drugs with opioid analgesics (see 9.2 Drug Interactions Overview). If the decision is made to prescribe a benzodiazepine or other CNS depressant concomitantly with an opioid analgesic, prescribe the lowest effective dosages and minimum durations of concomitant use. In patients already receiving an opioid analgesic, prescribe a lower initial dose of the benzodiazepine or other CNS depressant than indicated in the absence of an opioid, and titrate based on clinical response. If an opioid analgesic is initiated in a patient already taking a benzodiazepine or other CNS depressant, prescribe a lower initial dose of the opioid analgesic, and titrate based on clinical response. Follow patients closely for signs and symptoms of respiratory depression and sedation.
Advise both patients and caregivers about the risks of respiratory depression and sedation when CODEINE CONTIN is used with benzodiazepines or other CNS depressants (including alcohol and illicit drugs). Advise patients not to drive or operate heavy machinery until the effects of concomitant use of the benzodiazepine or other CNS depressant have been determined. Screen patients for risk of substance use disorders, including opioid abuse and misuse, and warn them of the risk for overdose and death associated with the use of additional CNS depressants including alcohol and illicit drugs (see 9.2 Drug Interactions Overview).
CODEINE CONTIN should not be consumed with alcohol as it may increase the chance of experiencing dangerous side effects, including death (see 2 Contraindications; 8.1 Adverse Reaction Overview, Sedation, and 9.3 Drug-Behaviour Interactions).
Severe pain antagonizes the subjective and respiratory depressant actions of opioid analgesics. Should pain suddenly subside, these effects may rapidly manifest.
Opioid Induced Hyperalgesia: Opioid induced hyperalgesia (OIH) is a paradoxical response to an opioid in which there is an increase in pain perception despite stable or increased opioid exposure. It differs from tolerance, in which higher opioid doses are required to achieve the same analgesic effect or treat recurring pain. Clinically, OIH may be associated with high opioid doses, long term opioid treatment, and intra-operative opioid use. OIH may manifest as an unexplained increase in pain, more diffuse pain than pre-existing, or as pain from ordinary (i.e., Non-painful stimuli (allodynia), in the absence of disease progression. When OIH is suspected, the dose of opioid should be reduced or tapered off, if possible. It is reasonable to consider opioid rotation, or the use of a Non-opioid strategy for pain control. There is currently No well-established treatment for OIH.
Use in Patients with Convulsive or Seizure Disorders: The codeine in CODEINE CONTIN may aggravate convulsions in patients with convulsive disorders and may induce or aggravate seizures in some clinical settings. Therefore, CODEINE CONTIN should not be used in these patients (see 2 Contraindications).
Serotonin Toxicity/Serotonin Syndrome: Serotonin toxicity also known as serotonin syndrome is a potentially life-threatening condition and has been reported with codeine, including CODEINE CONTIN, particularly during combined use with other serotonergic drugs (see 9.4 Drug-Drug Interactions, Serotonergic Agents).
Serotonin toxicity is characterised by neuromuscular excitation, autonomic stimulation (e.g. tachycardia, flushing) and altered mental state (e.g. anxiety, agitation, hypomania). In accordance with the Hunter Criteria, serotonin toxicity diagnosis is likely when, in the presence of at least one serotonergic agent, one of the following is observed:
- Spontaneous clonus
- Inducible clonus or ocular clonus with agitation or diaphoresis
- Tremor and hyperreflexia
- Hypertonia and body temperature >38°C and ocular clonus or inducible clonus.
If concomitant treatment with CODEINE CONTIN and other serotonergic agents is clinically warranted, careful observation of the patient is advised, particularly during treatment initiation and dose increases (see 9.4 Drug-Drug Interactions, Serotonergic Agents). If serotonin toxicity is suspected, discontinuation of the serotonergic agents should be considered.
Head Injury: The respiratory depressant effects of codeine and the capacity to elevate cerebrospinal fluid pressure, may be greatly increased in the presence of an already elevated intracranial pressure produced by trauma. Also, codeine may produce confusion, miosis, vomiting and other side effects which obscure the clinical course of patients with head injury. In such patients, codeine should not be used (see 2 Contraindications).
Perioperative Considerations
CODEINE CONTIN is not indicated for pre-emptive analgesia (administration preoperatively for the management of post-operative pain).
In the case of planned chordotomy or other pain-relieving operations, patients should not be treated with CODEINE CONTIN for at least 24 hours before the operation and it should not be used in the immediate post-operative period.
Physicians should individualize treatment, moving from parenteral to oral analgesics as appropriate. Thereafter, if CODEINE CONTIN is to be continued after the patient recovers from the post-operative period a new dosage should be administered in accordance with the changed need for pain relief. The risk of withdrawal in opioid-tolerant patients should be addressed as clinically indicated.
The administration of analgesics in the peri-operative period should be managed by healthcare providers with adequate training and experience (e.g., by an anesthesiologist).
Codeine and other morphine-like opioids have been shown to decrease bowel motility. Ileus is a common post-operative complication, especially after intra-abdominal surgery with opioid analgesia. Caution should be taken to monitor for decreased bowel motility in post-operative patients receiving opioids. Standard supportive therapy should be implemented.
CODEINE CONTIN should not be used in the early post-operative period (12 to 24 hours post-surgery) unless the patient is ambulatory and gastrointestinal function is normal.
Renal
Dosage reduction is recommended in severe renal impairment due to the risk of toxicity (see 10.3 Pharmacokinetics, Special Populations and Conditions, Renal Insufficiency).
Codeine pharmacokinetics may be altered in patients with renal failure. Clearance may be decreased, and the metabolites may accumulate to much higher plasma levels in patients with renal failure as compared to patients with normal renal function. Start these patients cautiously with lower doses of CODEINE CONTIN or with longer dosing intervals and titrate slowly while carefully monitoring for side effects.
Reproductive Health
- Fertility
Long-term use of opioids may be associated with infertility (see 8.5 Post-Market Adverse Reactions).
- Function
Long-term use of opioids may be associated with decreased sex hormone levels and symptoms such as low libido or erectile dysfunction (see 8.5 Post-Market Adverse Reactions).
Respiratory
Respiratory Depression: Serious, life-threatening, or fatal respiratory depression has been reported with the use of opioids, even when used as recommended. Respiratory depression from opioid use, if not immediately recognized and treated, may lead to respiratory arrest and death. Management of respiratory depression may include close observation, supportive measures, and use of opioid antagonists, depending on the patient’s clinical status. Codeine should be used with extreme caution in patients with substantially decreased respiratory reserve, pre-existing respiratory depression, hypoxia or hypercapnia (see 2 Contraindications ).
While serious, life-threatening, or fatal respiratory depression can occur at any time during the use of CODEINE CONTIN, the risk is greatest during the initiation of therapy or following a dose increase. Patients should be closely monitored for respiratory depression when initiating therapy with CODEINE CONTIN and following dose increases.
Life-threatening respiratory depression is more likely to occur in the elderly, cachectic, or debilitated patients because they may have altered pharmacokinetics or altered clearance compared to younger, healthier patients.
To reduce the risk of respiratory depression, proper dosing and titration of CODEINE CONTIN are essential. Overestimating the CODEINE CONTIN dose when converting patients from another opioid product can result in a fatal overdose with the first dose. In these patients, the use of non-opioid analgesics should be considered, if feasible (see 7.1 Special Populations, Special Risk Groups, and 4 Dosage and Administration).
Respiratory depression and death have occurred in children who received codeine in the postoperative period following tonsillectomy and/or adenoidectomy and had evidence of being ultra-rapid metabolizers of codeine (i.e., multiple copies of the gene for cytochrome P450 isoenzyme 2D6 or high morphine concentrations).Children with obstructive sleep apnea who are treated with codeine for post-tonsillectomy and/or adenoidectomy pain may be particularly sensitive to the respiratory depressant effects of codeine that has been rapidly metabolized to morphine. Codeine-containing products are contraindicated for post-operative pain management in all pediatric patients undergoing tonsillectomy and/or adenoidectomy for obstructive sleep apnea syndrome (see 2 Contraindications).
Use in Patients with Chronic Pulmonary Disease: Monitor patients with significant chronic obstructive pulmonary disease or cor pulmonale, and patients having a substantially decreased respiratory reserve, hypoxia, hypercapnia, or preexisting respiratory depression for respiratory depression, particularly when initiating therapy and titrating with CODEINE CONTIN, as in these patients, even usual therapeutic doses of CODEINE CONTIN may decrease respiratory drive to the point of apnea. In these patients, use of alternative non-opioid analgesics should be considered, if possible. The use of CODEINE CONTIN is contraindicated in patients with acute or severe bronchial asthma, chronic obstructive airway, or status asthmaticus (see 2 Contraindications).
Sleep Apnea: Opioids can cause sleep-related breathing disorders such as sleep apnea syndromes (including central sleep apnea [CSA]) and hypoxia (including sleep-related hypoxia). Opioid use increases the risk of CSA in a dose-dependent manner. Evaluate patients on an ongoing basis for the onset of a new sleep apnea, or a worsening of an existing sleep apnea. In these patients, consider decreasing the total opioid dosage or stopping the opioid treatment if appropriate, using best practices for tapering of opioids (see 7 Warnings and Precautions, Dependence/Tolerance and/or Abuse Liability; 4.2 Recommended Dose and Dosage Adjustment, Adjustment or Reduction of Dosage).
7.1 Special Populations
Special Risk Groups: Codeine should be administered with caution to patients with a history of alcohol and drug abuse and in a reduced dosage to debilitated patients, and in patients with severely impaired pulmonary function, Addison’s disease, hypothyroidism, myxedema, toxic psychosis, prostatic hypertrophy or urethral stricture.
7.1.1 Pregnancy
CODEINE CONTIN is contraindicated in patients who are pregnant. Studies in humans have not been conducted. Codeine crosses the placental barrier and should not be administered to pregnant women unless in the judgement of the physician, potential benefits outweigh the risks.
Prolonged maternal use of opioids during pregnancy can result in withdrawal signs in the neonate. Neonatal Opioid Withdrawal Syndrome (NOWS), unlike opioid withdrawal syndrome in adults, may be life-threatening (see 7 Warnings and Precautions, Neonatal Opioid Withdrawal Syndrome (NOWS); 8 Adverse Reactions).
Use of CODEINE CONTIN is contraindicated in pregnant women (see 2 Contraindications).
Pregnant women using opioids should not discontinue their medication abruptly as this can cause pregnancy complication such as miscarriage or still-birth. Tapering should be slow and under medical supervision to avoid serious adverse events to the fetus.
7.1.2 Breastfeeding
Since opioids can cross the placental barrier and also excreted in breast milk, CODEINE CONTIN is contraindicated during labour, delivery, pregnancy and in nursing mothers. Life-threatening respiratory depression may occur in the infant if opioids are administered to the mother. Naloxone, a drug that counters the effects of opioids should be readily available if CODEINE CONTIN is used in this population.
CODEINE CONTIN is contraindicated in women who are breast-feeding (see 2 Contraindications). Codeine is secreted into human milk. In women with normal codeine metabolism (normal CYP2D6 activity), the amount of codeine secreted into human milk is low and dose-dependent. However, some women are ultra-rapid metabolizers of codeine (see 7 Warnings and Precautions, Endocrine and Metabolism, Risk of Death in Ultra-Rapid Metabolizers of Codeine). These women achieve higher-than-expected serum levels of codeine’s active metabolite, morphine, leading to higher-than-expected levels of morphine in breast milk and potentially dangerously high serum morphine levels in their breast-fed infants. Mothers using codeine should be informed about when to seek immediate medical care and how to identify the signs and symptoms of neonatal toxicity, such as drowsiness or sedation, difficulty breast-feeding, breathing difficulties, and decreased tone, in their baby. Therefore, maternal use of codeine can potentially lead to serious adverse reactions, including death in nursing infants.
Since there is a risk of infant exposure to codeine and morphine through breast milk, CODEINE CONTIN is contraindicated in breast-feeding. Prescribers should closely monitor mother-infant pairs and notify treating paediatricians about any use of codeine during breast-feeding.
7.1.3 Pediatrics
Pediatrics (<18 years of age):
Some children may be ultra-rapid metabolizers of codeine (see 7 Warnings and Precautions, Endocrine and Metabolism, Risk of Death in Ultra-Rapid Metabolizers of Codeine). Regardless of clinical setting, codeine (including CODEINE CONTIN) should not be used in children below the age of 12 years because of the risk of opioid toxicity due to the variable and unpredictable metabolism of codeine to morphine. CODEINE CONTIN has not been studied in the pediatric population, therefore the use of CODEINE CONTIN is not recommended in patients over 12 and under 18 years of age (See 2 Contraindications).
7.1.4 Geriatrics
Geriatrics (>65 years of age): In general, dose selection for an elderly patient should be cautious, usually starting at the low end of the dosing range, and titrated slowly reflecting the greater frequency of decreased hepatic, renal, or cardiac function, and of concomitant disease or other drug therapy (see 4.2 Recommended Dose and Dosage Adjustment, Geriatrics).
8 Adverse Reactions
8.1 Adverse Reaction Overview
Adverse effects of CODEINE CONTIN are similar to those of other opioid analgesics and represent an extension of pharmacological effects of the drug class. The major hazards of opioids include respiratory and central nervous system depression and to a lesser degree, circulatory depression, respiratory arrest, shock and cardiac arrest.
The most frequently observed adverse effects are constipation, dizziness, light-headedness, nausea, sedation, sweating and vomiting.
Sedation
Sedation is a common side effect of opioid analgesics, especially in opioid naïve individuals. Sedation may also occur partly because patients often recuperate from prolonged fatigue after the relief of persistent pain. Most patients develop tolerance to the sedative effects of opioids within three to five days and, if the sedation is not severe, will not require any treatment except reassurance. If excessive sedation persists beyond a few days, the dose of the opioid should be reduced and alternate causes investigated. Some of these are: concurrent CNS depressant medication, hepatic or renal dysfunction, brain metastases, hypercalcemia and respiratory failure. If it is necessary to reduce the dose, it can be carefully increased again after three or four days if it is obvious that the pain is not being well controlled. Dizziness and unsteadiness may be caused by postural hypotension, particularly in elderly or debilitated patients, and may be alleviated if the patient lies down.
Nausea and Vomiting
Nausea is a common side effect on initiation of therapy with opioid analgesics and is thought to occur by activation of the chemoreceptor trigger zone, stimulation of the vestibular apparatus and through delayed gastric emptying. The prevalence of nausea declines following continued treatment with opioid analgesics. When instituting therapy with an opioid for chronic pain, the routine prescription of an antiemetic should be considered. In the cancer patient, investigation of nausea should include such causes as constipation, bowel obstruction, uremia, hypercalcemia, hepatomegaly, tumor invasion of celiac plexus and concurrent use of drugs with emetogenic properties. Persistent nausea which does not respond to dosage reduction may be caused by opioid-induced gastric stasis and may be accompanied by other symptoms including anorexia, early satiety, vomiting and abdominal fullness. These symptoms respond to chronic treatment with gastrointestinal prokinetic agents.
Constipation
Practically all patients become constipated while taking opioids on a chronic basis. In some patients, particularly the elderly or bedridden, fecal impaction may result. It is essential to caution the patients in this regard and to institute an appropriate regimen of bowel management at the start of prolonged opioid therapy. Stimulant laxatives, stool softeners and other appropriate measures should be used as required. As fecal impaction may present as overflow diarrhea, the presence of constipation should be excluded in patients on opioid therapy prior to initiating treatment for diarrhea.
8.3 Less Common Clinical Trial Adverse Reactions
The following adverse effects occur less frequently with CODEINE CONTIN and opioid analgesics, whether related or not to codeine controlled release tablets.
| Cardiac disorders: | bradycardia, palpitation, tachycardia |
|---|---|
| Eye disorders: | blurred vision, diplopia, miosis, visual impairment |
| Gastrointestinal disorders: | abdominal pain, diarrhea, dry mouth |
General disorders and administration site reactions: Hepatobiliary disorders: | chills biliary spasm |
Nervous System Disorders: Metabolism and nutrition disorders: Musculoskeletal and connective tissue disorders: | headache, increased intracranial pressure, nystagmus, paresthesia, tremor, coordination abnormal, dizziness, syncope, taste altered anorexia muscle rigidity |
| Psychiatric disorders: | mood altered (nervousness, apprehension, depression, floating feelings, dreams), dysphoria, euphoria, hallucinations, disorientation, agitation, insomnia |
| Renal and urinary disorders: | urinary retention, urinary hesitancy |
| Respiratory, thoracic and mediastinal disorders: | bronchospasm, laryngospasm, obstructive sleep apnea syndrome |
Skin and subcutaneous tissue disorders: Vascular disorders: | diaphoresis, skin rash, pruritus, urticaria facial flushing, hypertension, hypotension |
|---|
8.5 Post-Market Adverse Reactions
The following adverse reactions have been identified during post approval use of codeine. Because these reactions are reported voluntarily from a population of uncertain size, it is not always possible to reliably estimate their frequency or establish a causal relationship to drug exposure.
Androgen deficiency: Chronic use of opioids may influence the hypothalamic-pituitary-gonadal axis, leading to androgen deficiency that may manifest as low libido, impotence, erectile dysfunction, amenorrhea, or infertility. The causal role of opioids in the clinical syndrome of hypogonadism is unknown because the various medical, physical, lifestyle, and psychological stressors that may influence gonadal hormone levels have not been adequately controlled for in studies conducted to date. Patients presenting with symptoms of androgen deficiency should undergo laboratory evaluation.
Hypoglycemia: Cases of hypoglycemia have been reported in patients taking opioids. Most reports were in patients with at least one predisposing risk factor (e.g., diabetes).
9 Drug Interactions
9.1 Serious Drug Interactions
|
|---|
9.2 Drug Interactions Overview
Interactions with CNS Depressants (including benzodiazepines and alcohol)
Due to additive pharmacologic effect, the concomitant use of benzodiazepines or other CNS depressants (e.g. other opioids, sedatives, gabapentinoids such as pregabalin, baclofen, hypnotics, antidepressants, anxiolytics, tranquilizers, muscle relaxants, general anesthetics, antipsychotics, phenothiazines, neuroleptics, antihistamines, antiemetics, and alcohol) and beta-blockers, increases the risk of respiratory depression, profound sedation, coma, and death. Reserve concomitant prescribing of these drugs for use in patients for whom alternative treatment options are inadequate. Limit dosages and durations to the minimum required. Follow patients closely for signs of respiratory depression and sedation (see 7 Warnings and Precautions, Neurologic, Interactions with CNS Depressants including benzodiazepines and alcohol). CODEINE CONTIN should not be consumed with alcohol as it may increase the chance of experiencing dangerous side effects.
9.3 Drug-Behaviour Interactions
The concomitant use of alcohol should be avoided (see 7 Warnings and Precautions, General).
9.4 Drug-Drug Interactions
The drugs listed in this table are based on either drug interaction case reports or studies, or potential interactions due to the expected magnitude and seriousness of the interaction (i.e., those identified as contraindicated).
Table 4 - Established or Potential Drug-Drug Interactions
| Proper/Common name | Source of Evidence | Effect | Clinical comment |
| Drugs Metabolized by CYP2D6 | C | Codeine is converted to morphine by the hepatic cytochrome CYP2D6, hence its safety and efficacy is controlled by this polymorphism, and has a high degree of variability in humans. | Given the higher potency of morphine to codeine, CYP2D6 activity levels have been associated with outcomes from codeine administration that range from an absence of effect to responses with the potential of serious medical consequences. CODEINE CONTIN is contraindicated in CYP2D6 ultra-rapid metabolizers (see 2 Contraindications; 7 Warnings and Precautions, Endocrine and Metabolism, Risk of Death in Ultra-Rapid Metabolizers of Codeine). |
| Inhibitors of CYP2D6 | CT | Metabolism of codeine may be inhibited. | About 5-10 percent of Caucasians and 1 percent of Asians exhibit the poor metabolizer phenotype. However, a range of CYP2D6 activity levels, including very efficient metabolizers of codeine, have been documented (See 7 Warnings and Precautions, Endocrine and Metabolism, Risk of Death in Ultra-Rapid Metabolizers of Codeine) Caution is recommended. |
| Proper/Common name | Source of Evidence | Effect | Clinical comment |
| Mixed Activity Agonist/Antagonist Opioids (e.g., pentazocine, nalbuphine, butorphanol, and buprenorphine) | T | Mixed agonist/antagonist analgesics may reduce the analgesic effect of codeine and/or may precipitate withdrawal symptoms in these patients. | Mixed agonist/antagonist opioid analgesics should be administered with caution to a patient who has received or is receiving a course of therapy with a pure opioid agonist analgesic such as codeine. |
| Monoamine Oxidase Inhibitors (MAOIs) | T | MAOIs intensify the effects of opioid drugs which can cause anxiety, confusion and decreased respiration. | CODEINE CONTIN is contraindicated in patients receiving MAOIs or who have taken them within the previous 14 days (see 2 Contraindications; 9.1 Serious Drug Interactions). |
| Serotonergic Agents (e.g. SSRI or SNRI) | C | Coadministration with CODEINE CONTIN may increase the risk of serotonin syndrome, a potentially life-threatening condition. (See 7 Warnings and Precautions, Neurologic, Serotonin Toxicity/Serotonin Syndrome) | If serotonin toxicity is suspected, discontinuation of the serotonergic agents should be considered. |
| Warfarin and other coumarin anticoagulants | T | Codeine may increase the anticoagulant activity of coumarin and other anticoagulants. | Monitor for increasing INR and consider dose reduction or discontinuation of CODEINE CONTIN. |
Legend: C = Case Study; CT = Clinical Trial; T = Theoretical; PBPK = Physiologically based pharmacokinetic modeling; popPK = Population pharmacokinetic modeling
9.5 Drug-Food Interactions
In the presence of food, the extent of absorption of CODEINE CONTIN is not significantly increased but peak concentrations are somewhat delayed, occurring at 3.9 - 4.5 hours post-dose.
9.6 Drug-Herb Interactions
Interactions with herbal products have not been established.
9.7 Drug-Laboratory Test Interactions
Interactions with laboratory tests have not been established.
10 Clinical Pharmacology
10.1 Mechanism of Action
Codeine is an opioid analgesic which exerts an agonist effect at specific, saturable opioid receptors in the CNS and other tissues. In man, codeine produces a variety of effects including analgesia, constipation from decreased gastrointestinal motility, suppression of the cough reflex, respiratory depression from reduced responsiveness of the respiratory center to carbon dioxide (CO2), nausea and vomiting via stimulation of the CTZ, changes in mood including euphoria and dysphoria, sedation, mental clouding, miosis and alterations of the endocrine and autonomic nervous systems.
10.2 Pharmacodynamics
Codeine and related opioids produce their major effects on the CNS and bowel by acting as agonists at specific saturable opioid receptors in the CNS and other tissues, particularly at the mµ receptors. The mechanism of action of opioids for analgesia is not at peripheral loci but rather at the level of the spinal cord and higher nerve centers where they are thought to alter the transmission of nerve impulses. The antitussive properties of codeine may be exerted not through the mµ receptors but other receptors that are not naloxone sensitive.
It has been speculated that the analgesic effectiveness of codeine is mediated partially by morphine, which is a metabolite of codeine. However, recent studies identifying endogenous formation of codeine and binding of codeine and its metabolites to mu receptors are supportive of an analgesic effect of codeine itself.
Orally administered codeine is approximately 60% as potent as intramuscular codeine in terms of total analgesia. The relative potency of codeine phosphate administered intramuscularly is approximately 1/12 that of intramuscularly administered morphine sulfate and orally, 200 mg of codeine phosphate is equivalent to 20 - 30 mg of morphine sulfate during chronic dosing.
Cardiovascular System: Codeine may produce release of histamine with or without associated peripheral vasodilation. Manifestations of histamine release and/or peripheral vasodilatation may include pruritus, flushing, red eyes, hyperhidrosis and/or orthostatic hypotension.
Central Nervous System: Codeine produces respiratory depression by direct action on brain stem respiratory centres. The respiratory depression involves both a reduction in the responsiveness of the brain stem centres to increases in carbon dioxide (CO2) tension and to electrical stimulation.
Codeine depresses the cough reflex by direct effect on the cough centre in the medulla. Antitussive effects may occur with doses lower than those usually required for analgesia.
Codeine causes miosis, even in total darkness. Pinpoint pupils are a sign of opioid overdose but are not pathognomonic (e.g., pontine lesions of hemorrhagic or ischemic origin may produce similar findings). Marked mydriasis rather than miosis may be seen with hypoxia in the setting of codeine overdose.
Endocrine System: Opioids may influence the hypothalamic-pituitary-adrenal or -gonadal axes. Some changes that can be seen include an increase in serum prolactin, and decreases in plasma cortisol and testosterone. Clinical signs and symptoms may be manifest from these hormonal changes.
Gastrointestinal Tract and Other Smooth Muscle: Codeine causes a reduction in motility associated with an increase in smooth muscle tone in the antrum of the stomach and duodenum. Digestion of food in the small intestine is delayed and propulsive contractions are decreased. Propulsive peristaltic waves in the colon are decreased, while tone may be increased to the point of spasm resulting in constipation. Other opioid-induced effects may include a reduction in gastric, biliary and pancreatic secretions, spasm of the sphincter of Oddi, and transient elevations in serum amylase.
Hepatobiliary System: Opioids may induce biliary spasm.
Immune System: In vitro and animal studies indicate that opioids have a variety of effects on immune functions, depending on the context in which they are used. The clinical significance of these findings is unknown.
10.3 Pharmacokinetics
Absorption: Codeine is readily absorbed from the gastrointestinal tract and has an oral bioavailability of 53%, relative to the intramuscular route.
CODEINE CONTIN is absorbed to an equivalent extent as immediate-release tablet or liquid formulations of codeine. In single dose studies in fasting, healthy volunteers, the maximum plasma codeine concentration (Cmax) is approximately 56% of that from immediate-release formulations and is achieved approximately 2.6 times later - at 3.3 hours post-dosing. In steady-state studies in healthy volunteers, both the extent of absorption and maximum plasma codeine concentrations are equivalent to those from immediate-release formulations at the same total daily dose. In the presence of food, the extent of absorption of CODEINE CONTIN is not significantly increased but peak concentrations are somewhat delayed, occurring at 3.9 - 4.5 hours post-dose.
Distribution: Codeine is rapidly distributed from blood to body tissues, passes the blood-brain barrier and is found in fetal tissue and breast milk. Codeine is metabolized in the liver to morphine and norcodeine, each representing about 10% of the administered dose of codeine.
Metabolism: Codeine is metabolized in the liver to morphine and norcodeine, each representing about 10% of the administered dose of codeine. Codeine is converted to morphine by the hepatic cytochrome CYP2D6, hence its safety and efficacy is controlled by this polymorphism, and has a high degree of variability in humans. CYP2D6 activity levels have been associated with outcomes from codeine administration that range from an absence of effect to responses with the potential of serious medical consequences (see 9.4 Drug-Drug Interactions).
Elimination: Urinary excretion products are free and glucuronide-conjugated codeine (about 70%), free and conjugated morphine (about 10%), normorphine (under 4%) and hydrocodone (<1%). The remainder of the dose appears in the feces.
Special Populations and Conditions
- Pediatrics: Some children may be ultra-rapid metabolizers of codeine (see 7 Warnings and Precautions, Endocrine and Metabolism, Risk of Death in Ultra-Rapid Metabolizers of Codeine). Regardless of clinical setting, codeine (including CODEINE CONTIN) should not be used in children below the age of 12 years because of the risk of opioid toxicity due to the variable and unpredictable metabolism of codeine to morphine. CODEINE CONTIN has not been studied in the pediatric population, therefore the use of CODEINE CONTIN is not recommended in patients over 12 and under 18 years of age. (See 2 Contraindications).
- Geriatrics: Codeine should be administered with caution, and in reduced dosages, to elderly or debilitated patients. Respiratory depression has occurred in the elderly following administration of large initial doses of opioids to patients who were not opioid-tolerant or when opioids were co-administered with other agents that can depress respiration. CODEINE CONTIN should be initiated at a low dose and slowly titrated to effect (see 7.1.4 Geriatrics).
- Sex: No data available.
- Pregnancy and breastfeeding: Codeine crosses the placental barrier and is found in fetal tissue and breast milk (see 2 Contraindications; 7.1.1 Pregnancy; 7.1.2 Breastfeeding).
- Genetic Polymorphism: Some individuals may be ultra-rapid metabolizers of codeine due to a specific CYP2D6 genotype (see Ethnic origin below and 7 Warnings and Precautions, Endocrine and Metabolism, Risk of Death in Ultra-Rapid Metabolizers of Codeine).
- Ethnic origin: About 5-10 percent of Caucasians and 1 percent of Asians exhibit the poor metabolizer phenotype and do not convert codeine to morphine sufficiently to benefit from the analgesic effect of the drug (see 9.4 Drug-Drug Interactions). However, some individuals may be ultra-rapid metabolizers of codeine due to a specific CYP2D6 genotype. These individuals convert codeine into its active metabolite, morphine, more rapidly and completely than other people leading to higher-than-expected serum morphine levels. The prevalence of this CYP2D6 phenotype varies widely and has been estimated at 0.5 to 1% in Chinese, Japanese and Hispanics, 1 to 10% in Caucasians, 3% in African Americans, and 16 to 28% in North Africans, Ethiopians, and Arabs. Data are not available for other ethnic groups (see 7 Warnings and Precautions, Endocrine and Metabolism, Risk of Death in Ultra-Rapid Metabolizers of Codeine).
- Hepatic Insufficiency: As formal studies have not been conducted in patients with hepatic impairment, the pharmacokinetics of codeine in this patient population are unknown. Therefore, these patients should be started cautiously with lower doses of CODEINE CONTIN or with longer dosing intervals and titrate slowly while carefully monitoring for side effects. Dosage reduction is recommended in severe hepatic impairment due to the risk of toxicity.
Renal Insufficiency: Codeine pharmacokinetics may be altered in patients with renal failure. Clearance may be decreased and the metabolites may accumulate to much higher plasma levels in patients with renal failure as compared to patients with normal renal function. Start these patients cautiously with lower doses of CODEINE CONTIN or
11 Storage, Stability, and Disposal
Store at room temperature (15°C - 30°C).
Disposal
CODEINE CONTIN should never be disposed of in household trash. Disposal via a pharmacy take back program is recommended. Unused or expired CODEINE CONTIN should be properly disposed of as soon as it is no longer needed to prevent accidental exposure to others, including children or pets. CODEINE CONTIN should not be shared with others and steps should be taken to protect it from theft or misuse. The patient should speak to their pharmacist about temporary storage options, if required, until the medication can be returned to the pharmacy for safe disposal.
12 Special Handling Instructions
CODEINE CONTIN should be kept in a safe place, such as under lock and out of the sight and reach of children before, during and after use. CODEINE CONTIN should not be used in front of children, since they may copy these actions.
Part 2: Scientific Information
13 Pharmaceutical Information
Drug Substance
Non-proprietary name of the drug substance: Codeine Monohydrate
Chemical name: 7, 8-Didehydro-4, 5α-epoxy-3-methoxy-17-methylmorphinan-6α-ol monohydrate
Molecular formula and molecular mass: C18H21NO3 • H2O / 317.38
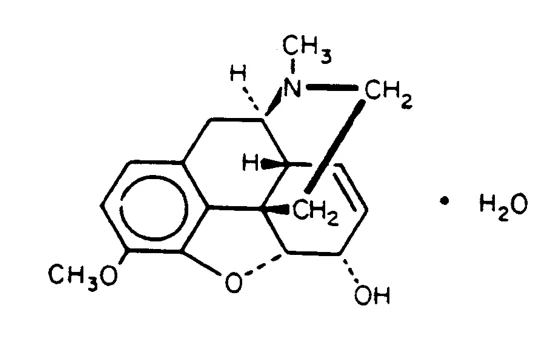
Structural formula:
Physicochemical properties:
Appearance: Colourless or white crystals or white, crystalline powder.
Solubility: Slightly soluble in water, very soluble in chloroform and freely soluble in ether.
Melting Point: 154° - 158°C.
Non-proprietary name of the drug substance: Codeine Sulfate Trihydrate
Chemical Name: 7, 8-Didehydro-4, 5α-epoxy-3-methoxy-17-methylmorphinan-6α-ol sulfate trihydrate
Molecular Formula and Molecular Mass: (C18H21NO3)2• H2SO4 •3H20 / 750.87
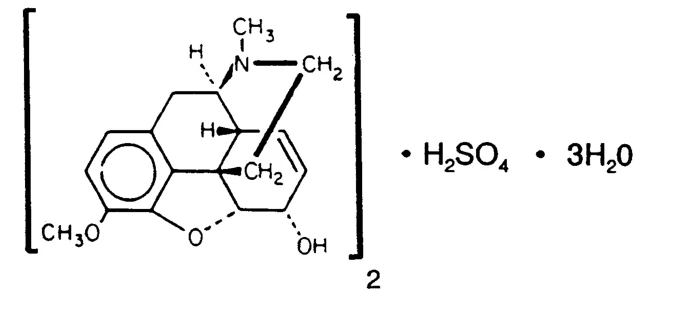
Structural Formula:
Physicochemical Properties:
Appearance: White crystals or white, crystalline powder.
Solubility: Slightly soluble in water, freely soluble in water at 80°C, very slightly soluble in alcohol, insoluble in chloroform and in ether.
Melting Point: 278°C (anhydrous)
14 Clinical Trials
The analgesic efficacy of CODEINE CONTIN has been evaluated in multiple dose studies in patients with cancer pain and chronic non-malignant pain. In a dose-response study in cancer patients, CODEINE CONTIN 150 mg every 12 hours provided approximately equivalent analgesia to 600 mg acetaminophen plus 60 mg codeine every 6 hours. In patients with cancer pain and chronic non-malignant pain receiving q4h as need (p.r.n.) acetaminophen plus codeine, CODEINE CONTIN (100, 150 or 200 mg every 12 hours) produced improved pain control and reduced consumption of supplementary acetaminophen plus codeine. In patients with chronic low back pain, CODEINE CONTIN (100 mg every 12 hours), supplemented with p.r.n. plain acetaminophen, produced lower pain scores and less fluctuation in pain throughout the day than p.r.n. acetaminophen plus codeine.
16 Non-Clinical Toxicology
General Toxicology: The LD50 of oral codeine in mice and rats, as determined by 15 different investigators, was between 237-640 mg/kg.
Carcinogenicity: No adequate long-term studies have been conducted in animals to determine whether codeine has a potential for carcinogenesis.
Reproductive and Developmental Toxicology: Animal studies with a number of opioids, including codeine, have indicated the possibility of teratogenic effect.