


Product Monograph - Dexlansoprazole (Altius Healthcare)
RECENT MAJOR LABEL CHANGES
No major label changes during the past 24 months.
TABLE OF CONTENTS
Sections or subsections that are not applicable at the time of authorization are not listed.
RECENT MAJOR LABEL CHANGES .......................................................................................... 2
TABLE OF CONTENTS ............................................................................................................ 2
PART I: HEALTH PROFESSIONAL INFORMATION .................................................................... 4
1 INDICATIONS ............................................................................................................. 4
1.1 Pediatrics .................................................................................................................. 4
1.2 Geriatrics .................................................................................................................. 4
2 CONTRAINDICATIONS ................................................................................................ 4
4 DOSAGE AND ADMINISTRATION ................................................................................ 4
4.1 Dosing Considerations ............................................................................................. 4
4.2 Recommended Dose and Dosage Adjustment ........................................................ 5
4.4 Administration ......................................................................................................... 5
4.5 Missed Dose ............................................................................................................. 6
5 OVERDOSAGE ............................................................................................................ 6
6 DOSAGE FORMS, STRENGTHS, COMPOSITION AND PACKAGING ................................ 6
7 WARNINGS AND PRECAUTIONS ................................................................................. 7
7.1 Special Populations .................................................................................................. 9
7.1.1 Pregnant Women ............................................................................................... 9
7.1.2 Breast-feeding .................................................................................................... 9
7.1.3 Pediatrics ............................................................................................................ 9
7.1.4 Geriatrics .......................................................................................................... 10
8 ADVERSE REACTIONS............................................................................................... 10
8.1 Adverse Reaction Overview ................................................................................... 10
8.2 Clinical Trial Adverse Reactions ............................................................................. 10
8.2.1 Clinical Trial Adverse Reactions – Pediatrics.................................................... 11
8.3 Less Common Clinical Trial Adverse Reactions ..................................................... 12
8.5 Post-Market Adverse Reactions ............................................................................. 13
9 DRUG INTERACTIONS .............................................................................................. 14
9.4 Drug-Drug Interactions .......................................................................................... 14
9.5 Drug-Food Interactions .......................................................................................... 17
9.6 Drug-Herb Interactions .......................................................................................... 17
9.7 Drug-Laboratory Test Interactions......................................................................... 17
10 CLINICAL PHARMACOLOGY ...................................................................................... 17
10.1 Mechanism of Action ....................................................................................... 17
10.2 Pharmacodynamics .......................................................................................... 18
10.3 Pharmacokinetics ............................................................................................. 19
11 STORAGE, STABILITY AND DISPOSAL ........................................................................ 23
12 SPECIAL HANDLING INSTRUCTIONS .......................................................................... 23
PART II: SCIENTIFIC INFORMATION ..................................................................................... 24
13 PHARMACEUTICAL INFORMATION .......................................................................... 24
14 CLINICAL TRIALS ...................................................................................................... 24
14.1 Efficacy and Safety Studies .............................................................................. 24
14.2 Study Results .................................................................................................... 27
15 MICROBIOLOGY ...................................................................................................... 31
16 NON-CLINICAL TOXICOLOGY .................................................................................... 31
PATIENT MEDICATION INFORMATION ................................................................................ 34
PART I: HEALTH PROFESSIONAL INFORMATION
1 INDICATIONS
DEXLANSOPRAZOLE (dexlansoprazole delayed release capsules) is indicated for:
- healing of all grades of erosive esophagitis (EE) for up to 8 weeks in patients 12 years of age and older.
- maintaining healing of erosive esophagitis for up to 4 months in adolescents 12 to 17 years of age and up to 6 months in adults.
- the treatment of heartburn associated with symptomatic non-erosive gastroesophageal reflux disease (GERD) for 4 weeks in patients 12 years of age and older.
1.1 Pediatrics
- Pediatrics (12 to 17 years of age): Based on the data submitted and reviewed by Health Canada, the safety and efficacy of DEXLANSOPRAZOLE in pediatric patients aged 12 to 17 years has been established. Therefore, Health Canada has authorized all indications for pediatric use in this age group. See 14.2 Study Results.
- Pediatrics (<12 years of age): Based on the data submitted and reviewed by Health Canada, the safety and efficacy of DEXLANSOPRAZOLE in pediatric patients aged less than 12 years has not been established; therefore, Health Canada has not authorized an indication for pediatric use in this age group. See 7.1.3 Pediatrics.
1.2 Geriatrics
- Geriatrics (>65 years of age): Based on the data submitted and reviewed by Health Canada, the safety and efficacy of DEXLANSOPRAZOLE in geriatric patients has been established. Therefore, Health Canada has authorized all indications for geriatric use. No dosage adjustment is necessary for elderly patients. See 7.1.4 Geriatrics.
2 CONTRAINDICATIONS
- DEXLANSOPRAZOLE is contraindicated in patients who are hypersensitive to this drug or to any ingredient in the formulation, including any non-medicinal ingredient, or component of the container. For a complete listing, see 6 DOSAGE FORMS, STRENGTHS, COMPOSITION AND PACKAGING.
DEXLANSOPRAZOLE is contraindicated with co-administration of rilpivirine. See 7 WARNINGS AND
PRECAUTIONS and 9 DRUG INTERACTIONS.
4 DOSAGE AND ADMINISTRATION
4.1 Dosing Considerations
- Patients should use the lowest dose and shortest duration of PPI therapy appropriate to the condition being treated.
- Withdrawal of long-term PPI therapy can lead to aggravation of acid related symptoms and may result in rebound acid hypersecretion.
4.2 Recommended Dose and Dosage Adjustment
| Indication | Recommended Dose, Route of | Frequency | ||
| administration | ||||
| Healing of Erosive Esophagitis | 60 mg, Oral or Nasogastric | Once daily for up to 8 weeks | ||
| Maintenance of Healed Erosive Esophagitis | 30 mg a, Oral or Nasogastric | Once daily for up to 6 months in adults and 4 months in adolescents (12 to 17 years) b | ||
| Symptomatic Non-Erosive Gastroesophageal Reflux Disease (GERD) | 30 mg, Oral or Nasogastric | Once daily for 4 weeks | ||
a In patients who had moderate or severe erosive esophagitis, a maintenance dose of 60 mg may be used. b Controlled studies did not extend beyond 6 months in adults, and beyond 4 months in adolescents 12 to 17 years of age.
- No dosage adjustment for DEXLANSOPRAZOLE is necessary for patients with mild hepatic impairment (Child-Pugh Class A). DEXLANSOPRAZOLE 30 mg should be considered for patients with moderate hepatic impairment (Child-Pugh Class B). No studies have been conducted in patients with severe hepatic impairment (Child-Pugh Class C).
- No dosage adjustment is necessary for elderly patients or for patients with renal impairment.
- Health Canada has not authorized an indication for pediatric use in patients less than 12 years of age. See 7.1.3 Pediatrics.
4.4 Administration
DEXLANSOPRAZOLE can be taken without regard to food or the timing of food.
DEXLANSOPRAZOLE should be swallowed whole with plenty of water.
- Alternatively, DEXLANSOPRAZOLE capsules can be opened and administered as follows:
Administration with Applesauce
- 1. Place one tablespoon of applesauce into a clean container
- 2. Open capsule
- 3. Sprinkle intact granules on applesauce;
- 4. Swallow applesauce and granules immediately. Do not chew granules. Do not save the applesauce and granules for later use.
Administration with Water in an Oral Syringe
- 1. Open the capsule and empty the granules into a clean container with 20 mL of water.
- 2. Withdraw the entire mixture into a syringe.
- 3. Gently swirl the syringe in order to keep granules from settling.
- 4. Administer the mixture immediately into the mouth. Do not save the water and granule mixture for later use.
- 5. Refill the syringe with 10 mL of water, swirl gently, and administer.
- 6. Repeat step 5.
Administration with Water via a Nasogastric Tube (≥16 French)
- 1. Open the capsule and empty the granules into a clean container with 20 mL of water.
- 2. Withdraw the entire mixture into a catheter-tip syringe.
- 3. Swirl the syringe gently in order to keep the granules from settling, and immediately inject the mixture through the nasogastric tube into the stomach. Do not save the water and granule mixture for later use.
- 4. Refill the syringe with 10 mL of water, swirl gently, and flush the tube.
- 5. Repeat step 4.
4.5 Missed Dose
If a capsule is missed at its usual time, it should be taken as soon as possible. But if it is too close to the time of the next dose, only the prescribed dose should be taken at the appointed time. A double dose should not be taken.
5 OVERDOSAGE
There have been no reports of significant overdose of DEXLANSOPRAZOLE. Dexlansoprazole is not expected to be removed from the circulation by hemodialysis.
For management of a suspected drug overdose, contact your regional poison control centre.
6 DOSAGE FORMS, STRENGTHS, COMPOSITION AND PACKAGING
Table – Dosage Forms, Strengths, Composition and Packaging
DEXLANSOPRAZOLE is supplied as a dual delayed release formulation in capsules for oral administration using Dual Delayed Release technology. The capsules contain dexlansoprazole in a mixture of two types of enteric-coated granules with different pH-dependent dissolution profiles. One type of granule is designed to release dexlansoprazole after the granules reach the proximal small intestine; the second type of granule is designed to release dexlansoprazole in the distal region of the small intestine, generally several hours later.
DEXLANSOPRAZOLE is provided in high-density polyethylene (HDPE) bottles in 90 count configurations. Each 30 mg capsule is opaque, blue and gray with TAP and “30” imprinted on the capsule and each 60 mg capsule is opaque, blue with TAP and “60” imprinted on the capsule.
| Route of | Dosage Form / | Non-medicinal Ingredients | ||||
| Administration | Strength/Composition | |||||
| Oral, Nasogastric | Capsule (Delayed Release) 30 mg, 60 mg Dexlansoprazole | Capsule: colloidal silicon dioxide, hydroxypropyl cellulose, hypromellose 2910, low-substituted hydroxypropyl cellulose, magnesium carbonate, methacrylic acid copolymer, polyethylene glycol 8000, polysorbate 80, sucrose, sugar spheres, talc, titanium dioxide, and triethyl citrate. Capsule shell: carrageenan, hypromellose and potassium chloride. Based on the capsule shell color, blue contains FD&C Blue No. 2 aluminum lake; gray contains black ferric oxide; and both contain titanium dioxide. | ||||
7 WARNINGS AND PRECAUTIONS
General
Symptomatic response with dexlansoprazole does not preclude the presence of gastric malignancy.
Antibiotic Combination Therapy: Pseudomembranous colitis has been reported with nearly all antibacterial agents, including clarithromycin and amoxicillin, and may range in severity from mild to life threatening. Therefore, it is important to consider this diagnosis in patients who present with diarrhea subsequent to the administration of antibacterial agents.
Treatment with antibacterial agents alters the normal flora of the colon and may permit overgrowth of Clostridia. Studies indicate that a toxin produced by Clostridium difficile is a primary cause of “antibiotic-associated colitis”.
After the diagnosis of pseudomembranous colitis has been established, therapeutic measures should be initiated. Mild cases of pseudomembranous colitis usually respond to discontinuation of the drug alone. In moderate to severe cases, consideration should be given to management with fluids and electrolytes, protein supplementation, and treatment with an antibacterial drug clinically effective against Clostridium difficile colitis.
Clostridium Difficile-Associated Diarrhea: Decreased gastric acidity due to any means, including proton pump inhibitors (PPIs), increases gastric counts of bacteria normally present in the gastrointestinal tract. Treatment with proton pump inhibitors (PPIs) can lead to an increased risk of gastrointestinal infections such as Salmonella, Campylobacter and Clostridium difficile.
An increased risk for Clostridium difficile infection (CDI) and Clostridium difficile-associated diarrhea (CDAD) has been observed in association with PPI use in several observational studies. CDI/CDAD should be considered in the differential diagnosis for diarrhea that does not improve. Additional risk factors for CDI and CDAD include recent hospitalization, the use of antibiotics, old age and the presence of co-morbidities.
Patients should be prescribed PPIs at the lowest dose and for the shortest duration required for the condition being treated and be reassessed to ascertain whether continued PPI therapy remains beneficial.
Concomitant Use with Methotrexate: Literature suggests that concomitant use of PPIs with methotrexate (primarily at high dose) may elevate and prolong serum levels of methotrexate and/or its metabolite, possibly leading to methotrexate toxicities. A temporary withdrawal of the PPI may be considered in some patients receiving treatments with high dose methotrexate. See 9.4 Drug-Drug Interactions.
Carcinogenesis and Mutagenesis
Dexlansoprazole has shown genotoxic and carcinogenic potential in experimental animals. See 16 NON-CLINICAL TOXICOLOGY, Carcinogenicity.
Drug Interactions with Antiretroviral Drugs
PPIs have been reported to interact with some antiretroviral drugs. The clinical importance and the mechanisms behind these interactions are not always known. A change in gastric pH may change the absorption of the antiretroviral drug. Other possible mechanisms are via CYP 2Cl9. See 9.4 Drug-Drug Interactions.
Rilpivirine: Co-administration is contraindicated due to significant decrease in rilpivirine exposure and loss of therapeutic effect. See 2 CONTRAINDICATIONS.
Atazanavir and Nelfinavir: Co-administration with atazanavir or nelfinavir is not recommended due to decreased atazanavir and nelfinavir exposure (see the REYATAZ® and VIRACEPT® Product Monographs).
If the combination of dexlansoprazole with atazanavir is judged unavoidable, close clinical monitoring is recommended in combination with the use of 400 mg atazanavir/100 mg ritonavir dose; the dose of dexlansoprazole should not exceed an equivalent dose of omeprazole of 20 mg daily (see REYATAZ® Product Monograph).
Saquinavir: If dexlansoprazole is co-administered with saquinavir/ritonavir, caution and monitoring for potential saquinavir toxicities, including gastrointestinal symptoms, increased triglycerides, deep vein thrombosis and QT prolongation, are recommended. Dose reduction of saquinavir should be considered from the safety perspective for individual patients (see INVIRASE® Product Monograph).
Endocrine and Metabolism
Hypomagnesemia: Hypomagnesemia, symptomatic and asymptomatic, has been reported rarely in patients treated with PPIs for at least three months, in most cases after a year of therapy. Serious adverse events include tetany, arrhythmias, and seizures. Hypomagnesemia may lead to hypocalcemia and/or hypokalemia. See 8.5 Post-Market Adverse Reactions. In most patients, treatment of hypomagnesemia (and hypomagnesemia associated hypocalcemia and/or hypokalemia) required magnesium replacement and discontinuation of the PPI.
For patients expected to be on prolonged treatment or who take PPIs with medications such as digoxin or drugs that may cause hypomagnesemia (e.g., diuretics), health care professionals may consider monitoring magnesium levels prior to initiation of PPI treatment and periodically. See 8 ADVERSE REACTIONS.
The chronic use of PPIs may lead to hypomagnesemia.
Cyanocobalamin (Vitamin B12) Deficiency: The prolonged use of proton pump inhibitors may impair the absorption of protein-bound Vitamin B12 and may contribute to the development of cyanocobalamin (Vitamin B12) deficiency.
Gastrointestinal
Long-term use of dexlansoprazole is associated with an increased risk of fundic gland polyps, especially beyond one year. See 8.5 Post-Market Adverse Drug Reactions. Most fundic gland polyps are asymptomatic. Use the lowest dose and shortest duration of PPI therapy appropriate to the condition being treated.
Genitourinary
Testicular interstitial cell adenoma occurred in 1 of 30 rats treated with 50 mg/kg/day of lansoprazole (13 times the recommended human dose based on body surface area) in a one-year toxicity study. See 16 NON-CLINICAL TOXICOLOGY, Carcinogenicity.
These changes are associated with endocrine alterations which have not been, to date, observed in humans.
Hepatic/Biliary/Pancreatic
No dosage adjustment is necessary for patients with mild hepatic impairment (Child-Pugh Class A). A maximum daily dose of 30 mg should be considered for patients with moderate hepatic impairment
(Child-Pugh Class B). No studies have been conducted in patients with severe hepatic impairment. See 10.3 Special Populations and Conditions.
Immune
Subacute cutaneous lupus erythematosus: Subacute cutaneous lupus erythematosus (SCLE) has been reported with the use of PPIs. If lesions occur, especially in sun-exposed areas of the skin, and if accompanied by arthralgia, the patient should seek medical help promptly and the health care professional should consider stopping DEXLANSOPRAZOLE. The occurrence of SCLE with previous PPI treatment may increase the risk of SCLE with other PPIs. See 8.5 Post-Market Adverse Drug Reactions.
Monitoring and Laboratory Tests
During treatment with antisecretory drugs, chromogranin A (CgA) increases due to decreased gastric acidity. Increased CgA levels may interfere with investigations for neuroendocrine tumours. To avoid this interference, DEXLANSOPRAZOLE treatment should be stopped 14 days before CgA measurements. See 9.4 Drug-Drug Interactions.
Musculoskeletal
Bone Fracture: Several published observational studies suggest that PPI therapy may be associated with an increased risk for osteoporosis-related fractures of the hip, wrist, or spine. The risk of fracture was increased in patients who received high-dose, defined as multiple daily doses, and long-term PPI therapy (a year or longer). Patients should use the lowest dose and shortest duration of PPI therapy appropriate to the condition being treated. Patients at risk for osteoporosis-related fractures should be managed according to established treatment guidelines. See 4 DOSAGE AND ADMINISTRATION and 8 ADVERSE REACTIONS.
Renal
No dosage adjustment is necessary for patients with renal impairment. See 10.3 Special Populations and Conditions.
7.1 Special Populations
7.1.1 Pregnant Women
There are no adequate or well-controlled studies in pregnant women with DEXLANSOPRAZOLE. Exposure in clinical trials was very limited. DEXLANSOPRAZOLE should not be administered to pregnant women unless the expected benefits outweigh the potential risks. See 16 NON-CLINICAL TOXICOLOGY, Reproductive and Developmental Toxicology.
7.1.2 Breast-feeding
It is not known whether dexlansoprazole is excreted in human milk. However, lansoprazole (the racemate) and its metabolites are excreted in the milk of rats. As many drugs are excreted in human milk, DEXLANSOPRAZOLE should not be given to nursing mothers unless its use is considered essential. In this case nursing should be avoided.
7.1.3 Pediatrics
Pediatrics (<12 years of age): Based on the data submitted and reviewed by Health Canada, the safety and efficacy of DEXLANSOPRAZOLE in pediatric patients has not been established; therefore, Health Canada has not authorized an indication for pediatric use in children under 12 years of age.
DEXLANSOPRAZOLE should not be used in pediatric patients less than one year of age because lansoprazole (the racemic mixture) was not effective for the treatment of symptomatic GERD in a multicenter, double-blind controlled trial. In addition, toxicology studies with lansoprazole have shown heart valve thickening and bone changes in juvenile rats. See 16 NON-CLINICAL TOXICOLOGY, Juvenile Animal Toxicity Data.
Pediatrics (12 to 17 years of age): DEXLANSOPRAZOLE is indicated for adolescents 12 to 17 years of age, and is supported by evidence from adequate and well-controlled studies of dexlansoprazole in adults, and by additional efficacy, safety and pharmacokinetic data in adolescents 12 to 17 years of age for the treatment of heartburn associated with symptomatic non-erosive GERD, healing of all grades of EE, and maintenance of healed EE. See 8.2.1 Clinical Trial Adverse Reactions - Pediatrics, 14 CLINICAL TRIALS, and 10.3 Pharmacokinetics, Special Populations and Conditions.
7.1.4 Geriatrics
Geriatrics (>65 years of age): In clinical studies of DEXLANSOPRAZOLE, 11% of patients were aged 65 years and over. No overall differences in safety or effectiveness were observed between these patients and younger patients. No dosage adjustment is necessary for elderly patients. See 10.3 Special Populations and Conditions.
Benefits of use of PPIs should be weighed against the increased risk of fractures as patients in this category (> 71 years of age) may already be at high risk for osteoporosis-related fractures. If the use of PPIs is required, they should be managed carefully according to established treatment guidelines. See 7 WARNINGS AND PRECAUTIONS, Musculoskeletal and 8 ADVERSE REACTIONS.
8 ADVERSE REACTIONS
8.1 Adverse Reaction Overview
The most common adverse drug reactions (occurring in at least 1% of subjects) reported in adult patients treated with dexlansoprazole in placebo and positive-controlled trials were diarrhea, abdominal pain, headache, nausea, flatulence, and constipation. The adverse reaction profile observed in adolescent patients (12 to 17 years of age) was similar to that of adults.
8.2 Clinical Trial Adverse Reactions
Clinical trials are conducted under very specific conditions. The adverse reaction rates observed in the clinical trials; therefore, may not reflect the rates observed in practice and should not be compared to the rates in the clinical trials of another drug. Adverse reaction information from clinical trials is useful in identifying and approximating rates of adverse drug reactions in real-world use.
The safety of DEXLANSOPRAZOLE was evaluated in 4548 patients in controlled and uncontrolled clinical studies (30 mg, 60 mg, and 90 mg), including 863 patients treated for at least 6 months and 282 patients treated for one year. Patients ranged in age from 18 to 90 years (median age 48 years), with 54% female, 85% Caucasian, 8% Black, 4% Asian and 3% other races. Six randomized controlled clinical trials were conducted for the treatment of erosive esophagitis, maintenance of healed erosive esophagitis, and symptomatic GERD, which included 896 patients on placebo, 2621 patients on DEXLANSOPRAZOLE 30 mg or 60 mg and 1363 patients on lansoprazole 30 mg.
The following adverse events were reported to have a possible or definite treatment-relationship to DEXLANSOPRAZOLE in 1% or more of the treated patients in placebo and positive-controlled clinical trials (Tables 1 and 2, respectively). Numbers in parentheses indicate the percentage of the adverse events reported.
Table 1: Incidence of Possibly or Definitely Treatment-Related Adverse Events in Placebo Controlled
Studies
Body System Adverse Event | DEXLANSOPRAZOLE | Placebo (N=896) n (%) | ||
| 30 mg and 60 mg | ||||
| (N=1399) | ||||
| n (%) | ||||
Gastrointestinal disorders Diarrhea Abdominal Pain Nausea Flatulence Constipation | 52 (3.7) 37 (2.6) 31 (2.2) 25 (1.8) 15 (1.1) | 17 (1.9) 14 (1.6) 16 (1.8) 5 (0.6) 9 (1.0) | ||
Nervous system disorders Headache | 31 (2.2) | 21 (2.3) | ||
Table 2: Incidence of Possibly or Definitely Treatment-Related Adverse Events in Active Controlled
Clinical Trials
Body System Adverse Event | DEXLANSOPRAZOLE | Lansoprazole | ||||
| 60 mg and 90 mg | 30 mg | |||||
| (N=1374) | (N=1363) | |||||
| n (%) | n (%) | |||||
Gastrointestinal disorders Diarrhea Abdominal pain Nausea | 44 (3.2) 21 (1.5) 14 (1.0) | 28 (2.1) 19 (1.4) 18 (1.3) | ||||
Nervous system disorders Headache | 16 (1.2) | 19 (1.4) | ||||
In placebo-controlled studies, gastrointestinal adverse reactions other than constipation occurred at a higher incidence for DEXLANSOPRAZOLE than placebo. In active-controlled studies, diarrhea occurred at a higher incidence for DEXLANSOPRAZOLE than lansoprazole. The incidence of other common adverse reactions for DEXLANSOPRAZOLE were similar to or lower than placebo or lansoprazole.
8.2.1 Clinical Trial Adverse Reactions – Pediatrics
The safety of DEXLANSOPRAZOLE was evaluated in controlled and single-arm clinical trials including 166 adolescents, 12 to 17 years of age for the treatment of symptomatic non-erosive GERD, healing of EE, maintenance of healed EE and relief of heartburn. See 14.2 Study Results.
The adverse reaction profile was similar to that of adults. The most common adverse reactions that occurred in ≥ 5% of patients were headache, abdominal pain, diarrhea, nasopharyngitis and oropharyngeal pain.
8.3 Less Common Clinical Trial Adverse Reactions
Other adverse reactions that were reported for DEXLANSOPRAZOLE (30 mg, 60 mg or 90 mg) in controlled studies at an incidence of less than 1% are listed below by body system:
Blood and Lymphatic System
Disorders:
anemia, lymphadenopathy
Cardiac Disorders: acute myocardial infarction, angina, arrhythmia, bradycardia, edema, palpitations, tachycardia
Ear and Labyrinth Disorders: ear pain, tinnitus, vertigo
Endocrine Disorders: goiter
Eye Disorders: eye irritation, eye swelling
Gastrointestinal Disorders: abdominal discomfort, abdominal tenderness, abnormal feces, anal discomfort, Barrett’s esophagus, bezoar, bowel sounds abnormal, breath odor, colitis microscopic, colonic polyp, dry mouth, duodenitis, dyspepsia, dysphagia, enteritis, eructation, esophagitis, gastric polyp, gastritis, gastroenteritis, gastrointestinal disorders, gastrointestinal hypermotility disorders, GERD, GI ulcers and perforation, hematemesis, hematochezia, hemorrhoids, impaired gastric emptying, irritable bowel syndrome, mucus stools, oral mucosal blistering, painful defecation, paresthesia oral, proctitis, rectal hemorrhage, vomiting
General Disorders and
Administration Site
Conditions:
adverse drug reaction, asthenia, chest pain, chills, feeling abnormal, inflammation, mucosal inflammation, nodule, pain, pyrexia
Hepatobiliary Disorders: biliary colic, cholelithiasis, hepatomegaly Immune System Disorders: hypersensitivity
Infections and Infestations: candida infections, influenza, nasopharyngitis, oral herpes, pharyngitis, sinusitis, upper respiratory tract infection, viral infection, vulvo-vaginal infection
Injury, Poisoning and
Procedural Complications:
overdose, procedural pain, sunburn
Laboratory Investigations:
ALP increased, ALT increased, AST increased, bilirubin decreased/increased, blood creatinine increased, blood gastrin increased, blood glucose increased, blood potassium increased, liver function test abnormal, platelet count decreased, total protein increased, weight increased
Metabolism and Nutrition
Disorders:
appetite changes, hypercalcemia, hypokalemia
Musculoskeletal and
Connective Tissue
Disorders:
arthralgia, arthritis, muscle cramps, musculoskeletal pain, myalgia
Nervous System Disorders:
altered taste, convulsion, dizziness, memory impairment, migraine, paresthesia, psychomotor hyperactivity, tremor, trigeminal neuralgia Psychiatric Disorders: abnormal dreams, anxiety, depression, insomnia, libido changes Renal and Urinary Disorders: dysuria, micturition urgency
Reproductive System and
Breast Disorders:
dysmenorrhea, dyspareunia, menorrhagia, menstrual disorder
Respiratory, Thoracic and
Mediastinal Disorders:
aspiration, asthma, bronchitis, cough, dyspnoea, hiccups, hyperventilation, respiratory tract congestion, sore throat Skin and Subcutaneous Tissue
Disorders:
acne, dermatitis, erythema, pruritus, rash, skin lesion, urticaria
Vascular Disorders: deep vein thrombosis, hot flush, hypertension
Additional adverse reactions that were reported for DEXLANSOPRAZOLE (60 mg or 90 mg) in a long-term uncontrolled study included: anaphylaxis, auditory hallucination, B-cell lymphoma, bursitis, central obesity, cholecystitis acute, decreased hemoglobin, dehydration, diabetes mellitus, dysphonia, epistaxis, folliculitis, gout, herpes zoster, hyperglycemia, hyperlipidemia, hypothyroidism, increased neutrophils, MCHC decreased, neutropenia, oral soft tissue disorder, rectal tenesmus, restless legs syndrome, somnolence, thrombocythemia, tonsillitis.
8.5 Post-Market Adverse Reactions
Adverse reactions have been identified during post-marketing surveillance of DEXLANSOPRAZOLE. As these reactions are reported voluntarily from a population of uncertain size, it is not always possible to reliably estimate their frequency or establish a causal relationship to drug exposure.
Blood and Lymphatic System Disorders: autoimmune hemolytic anemia, idiopathic thrombocytopenic purpura
Ear and Labyrinth Disorders: deafness
Eye Disorders: blurred vision
Gastrointestinal Disorders: oral edema, fundic gland polyps (FGPs)†, pancreatitis, microscopic colitis
General Disorders and Administration
Site Conditions:
facial edema
Hepatobiliary Disorders: drug-induced hepatitis
Immune System Disorders:
anaphylactic shock (requiring emergency intervention), exfoliative dermatitis, Stevens-Johnson syndrome, subacute cutaneous lupus erythematosus (SCLE)†, toxic epidermal necrolysis (some fatal)
Metabolism and Nutritional Disorders: hypomagnesemia, hypocalcemia*, hypokalemia*, hyponatremia
Musculoskeletal and Connective Tissue: Osteoporosis and osteoporosis-related fractures
Nervous System Disorders: cerebrovascular accident, transient ischaemic attack Renal and Urinary Disorders: acute renal failure, Tubulointerstitial nephritis (TIN) Respiratory, Thoracic and Mediastinal
Disorders:
pharyngeal edema, throat tightness
Skin and Subcutaneous Tissue
Disorders:
DRESS syndrome (Drug Rash with Eosinophilia and Systemic Symptoms) (some fatal), generalized rash, leucocytoclastic vasculitis
* May be related to the occurrence of hypomagnesemia
† For further information, see 7 WARNINGS AND PRECAUTIONS
9 DRUG INTERACTIONS
9.4 Drug-Drug Interactions
The drugs listed in this table are based on either drug interaction case reports or studies, or potential interactions due to the expected magnitude and seriousness of the interaction (i.e., those identified as contraindicated).
Table 3- Established or Potential Drug-Drug Interactions
| Concomitant | Source of | Effect | Clinical comment | ||||
| Drug Name | Evidence | ||||||
| Antiretroviral Drugs | C | ↓ rilpivirine, atazanavir, nelfinavir ↑saquinavir | See 7 WARNINGS AND PRECAUTIONS, Drug Interactions with Antiretroviral Drugs Rilpivirine: Co-administration is contraindicated due to significant decrease in rilpivirine exposure and loss of therapeutic effect. See 2 CONTRAINDICATIONS. Atazanavir: Co-administration of dexlansoprazole with atazanavir is not recommended. Concomitant administration of omeprazole (20 or 40 mg once daily) substantially reduced plasma Cmax and AUC of atazanavir in healthy volunteers administered atazanavir or atazanavir/ritonavir. (see REYATAZ® Product Monograph). Nelfinavir: Co-administration of dexlansoprazole with nelfinavir is not recommended. Concomitant administration of omeprazole (40 mg daily) with nelfinavir (1250 mg twice daily) markedly reduced the AUC and Cmax for nelfinavir (by 36% and 37%, respectively) and its active metabolite M8 (by 92% and 89%, respectively) (see VIRACEPT® Product Monograph). Saquinavir: Co-administration of saquinavir requires caution and monitoring, along with potential dose reduction of saquinavir, due to increased saquinavir | ||||
| Concomitant | Source of | Effect | Clinical comment | ||||
| Drug Name | Evidence | ||||||
exposure and thus the risk of saquinavir-related toxicities (see the INVIRASE® Product Monograph). Concomitant administration of omeprazole (40 mg daily) with saquinavir/ritonavir (1000/100 mg twice daily) increased saquinavir AUC by 82% and Cmax by 75%. | |||||||
| Clopidogrel | CT | No clinically important effect | Concomitant administration of dexlansoprazole and clopidogrel in healthy subjects had no clinically important effect on exposure to the active metabolite of clopidogrel or clopidogrel-induced platelet inhibition. No dose adjustment of clopidogrel is necessary when administered with an approved dose of dexlansoprazole. Clopidogrel is metabolized to its active metabolite in part by CYP2C19. A study of healthy subjects who were CYP2C19 extensive metabolizers, receiving once daily administration of clopidogrel 75 mg alone or concomitantly with dexlansoprazole 60 mg (n=40), for 9 days was conducted. The mean AUC of the active metabolite of clopidogrel was reduced by approximately 9% (mean AUC ratio was 91%, with 90% CI of 86-97%) when dexlansoprazole was coadministered compared to administration of clopidogrel alone. Pharmacodynamic parameters were also measured and demonstrated that the change in inhibition of platelet aggregation (induced by 5 mcM ADP) was related to the change in the exposure to clopidogrel active metabolite. The clinical significance of this finding is not clear. | ||||
| Antacids | C | In studies of sucralfate administered concomitantly with lansoprazole: AUC ↓, Cmax ↓ | No formal drug-drug interaction studies were conducted with dexlansoprazole and antacids. Drug-drug interactions studies were performed with the racemate lansoprazole and antacids. Simultaneous administration of lansoprazole with aluminum and magnesium hydroxide or magaldrate results in lower peak plasma levels, but does not significantly reduce bioavailability. Antacids may be used concomitantly if required. In clinical trials, antacids were administered concomitantly with lansoprazole delayed-release capsules. In a single-dose crossover study when 30 mg of lansoprazole | ||||
| Concomitant | Source of | Effect | Clinical comment | ||||
| Drug Name | Evidence | ||||||
| was administered concomitantly with one gram of sucralfate in healthy volunteers, absorption of lansoprazole was delayed and its bioavailability was reduced. The value of lansoprazole AUC was reduced by 17% and that for Cmax was reduced by 21%. In a similar study when 30 mg of lansoprazole was administered concomitantly with 2 grams of sucralfate, lansoprazole AUC and Cmax were reduced by 32% and 55%, respectively. When lansoprazole dosing occurred 30 minutes prior to sucralfate administration, Cmax was reduced by only 28% and there was no statistically significant difference in lansoprazole AUC. Therefore, lansoprazole should be administered at least 30 minutes prior to sucralfate. It would be expected that similar results would be seen with dexlansoprazole. | |||||||
| Methotrexate | C | - | Case reports, published population pharmacokinetic studies, and retrospective analyses suggest that concomitant administration of PPIs and methotrexate (primarily at high dose) may elevate and prolong serum levels of methotrexate and/or its metabolite hydroxymethotrexate. However, no formal drug interaction studies of methotrexate with PPIs have been conducted. See 7 WARNINGS AND PRECAUTIONS. | ||||
| Tacrolimus | C | ↑ whole blood levels | Concomitant administration of dexlansoprazole and tacrolimus may increase whole blood levels of tacrolimus, especially in transplant patients who are intermediate or poor metabolizers of CYP2C19. | ||||
| Theophylline | CT | No established clinical effect | Although a study of the use of concomitant theophylline and dexlansoprazole did not reveal any changes in the pharmacokinetics or pharmacodynamics of theophylline, individual patients should monitor their theophylline level while taking the two drugs concomitantly. | ||||
| Warfarin | C, CT | ↑ INR and PT | In a study of 20 healthy subjects, co-administration of dexlansoprazole 90 mg once daily for 11 days with a single 25 mg oral dose of warfarin on day 6 did not result in any significant differences in the pharmacokinetics of warfarin or INR compared to administration of warfarin with placebo. However, there have been reports of increased INR and | ||||
| Concomitant | Source of | Effect | Clinical comment | ||||
| Drug Name | Evidence | ||||||
| prothrombin time in patients receiving PPIs and warfarin concomitantly. Patients treated with PPIs and warfarin concomitantly may need to be monitored for increases in INR and prothrombin time. | |||||||
Legend: C = Case Study; CT = Clinical Trial; T = Theoretical
Drugs with pH-Dependent Absorption Pharmacokinetics
It is theoretically possible that dexlansoprazole may interfere with the absorption of other drugs where gastric pH is an important determinant of oral bioavailability (e.g., Ampicillin esters, digoxin, iron salts, ketoconazole).
Cytochrome P 450 Interactions
dexlansoprazole is metabolized, in part, by CYP2C19 and CYP3A4. See 10.3 Pharmacokinetics, Metabolism.
In vitro studies have shown that dexlansoprazole is not likely to inhibit CYP isoforms 1A1, 1A2, 2A6, 2B6, 2C8, 2C9, 2D6, 2E1 or 3A4. As such, no clinically relevant interactions with drugs metabolized by these CYP enzymes would be expected. Furthermore, in vivo studies showed that dexlansoprazole did not have an impact on the pharmacokinetics of, coadministered phenytoin (CYP2C9 substrate) or theophylline (CYP1A2 substrate). The subjects’ CYP1A2 genotypes in the drug-drug interaction study with theophylline were not determined. Although in vitro studies indicated that dexlansoprazole has the potential to inhibit CYP2C19 in vivo, an in vivo drug-drug interaction study in mainly CYP2C19 extensive and intermediate metabolizers has shown that dexlansoprazole does not affect the pharmacokinetics of diazepam (CYP2C19 substrate).
9.5 Drug-Food Interactions
DEXLANSOPRAZOLE can be taken without regard to food or timing of food. See 10.3 Pharmacokinetics.
9.6 Drug-Herb Interactions
Interactions with herbal products have not been established.
9.7 Drug-Laboratory Test Interactions
During treatment with antisecretory drugs, Chromogranin A (CgA) increases due to decreased gastric acidity. Increased CgA levels may interfere with investigations for neuroendocrine tumours. To avoid this interference, DEXLANSOPRAZOLE treatment should be stopped 14 days before CgA measurements. See 10.2 Pharmacodynamics.
10 CLINICAL PHARMACOLOGY
10.1 Mechanism of Action
DEXLANSOPRAZOLE is a PPI that suppresses gastric acid secretion by specific inhibition of the (H+, K+)-ATPase in the gastric parietal cell. By acting specifically on the proton pump, dexlansoprazole blocks the final step of acid production.
10.2 Pharmacodynamics
Antisecretory Activity
The effects of DEXLANSOPRAZOLE 60 mg (n = 20) or lansoprazole 30 mg (n = 23) once daily for five days on 24-hour intragastric pH were assessed in healthy subjects in a multiple-dose crossover study. The results are summarized in Table 4.
Table 4- Effect on 24-Hour Intragastric pH on Day 5 After Administration of DEXLANSOPRAZOLE or
Lansoprazole
| DEXLANSOPRAZOLE | Lansoprazole | ||||
| 60 mg | 30 mg | ||||
| Mean Intragastric pH | |||||
| 4.55* | 4.13 | ||||
| % Time Intragastric pH > 4 (hours) | |||||
71* (17 hours) | 60 (14 hours) | ||||
* p value <0.05 versus lansoprazole.
In experimental animals, dexlansoprazole was more potent than lansoprazole in the suppression of basal and stimulated gastric acid secretion across five studies in pylorus-stimulated Sprague Dawley (SD) rats. In studies of basal secretion, histamine 2HCl-, bethanechol chloride-, pentagastrin- and 2 deoxy D glucose-stimulated secretion, lansoprazole demonstrated potency values which were 63, 50, 83, 31 and 63%, respectively, of those seen with dexlansoprazole. Lansoprazole was less potent and demonstrated a potency value which was 45% of that seen with dexlansoprazole following histamine-stimulated gastric acid secretion in Heidenham pouch male dogs.
Pharmacodynamic Properties: During treatment with antisecretory medicinal products, serum gastrin increases in response to the decreased acid secretion. Also CgA increases due to decreased gastric acidity. The increased CgA levels may interfere with investigations for neuroendocrine tumours. Available published evidence suggests that proton pump inhibitors should be discontinued 14 days prior to CgA measurements. This is to allow CgA levels that might be spuriously elevated following PPI treatment to return to reference range. See 7 WARNINGS AND PRECAUTIONS.
The effect of DEXLANSOPRAZOLE on serum gastrin concentrations was evaluated in approximately 3460 patients in clinical trials up to 8 weeks and in 1025 patients for up to 6 to 12 months. The mean fasting gastrin concentrations increased from baseline during treatment with DEXLANSOPRAZOLE 30 mg and 60 mg doses. In general, in patients treated for more than 6 months, mean serum gastrin levels increased during approximately the first 3 months of treatment and were stable for the remainder of treatment. Mean serum gastrin levels returned to pre-treatment levels within one month of discontinuation of treatment
Enterochromaffin-Like Cell (ECL) Effects: There were no reports of ECL cell hyperplasia in gastric biopsy specimens obtained from 857 patients treated with DEXLANSOPRAZOLE 30 mg, 60 mg or 90 mg for up to 12 months. See 16 NON-CLINICAL TOXICOLOGY, Carcinogenicity.
In male SD rats, dexlansoprazole was more potent than lansoprazole in suppression of lesion formation and alimentary tract injury across three studies. In studies examining indomethacin-induced gastric mucosal lesions, mepirizole-induced duodenal mucosal lesions and reflux esophagitis, lansoprazole demonstrated potency values which were 30, 29 and 37%, respectively, of those seen with
dexlansoprazole.
Cardiac electrophysiology
A study was conducted to assess the potential of DEXLANSOPRAZOLE to prolong the QT/QTc interval in healthy adult subjects. Dexlansoprazole doses of 90 mg or 300 mg did not delay cardiac repolarization compared to placebo. The positive control (moxifloxacin) produced statistically significantly greater mean maximum and time-averaged QT/QTc intervals compared to placebo.
10.3 Pharmacokinetics
Table 5- Mean (CV %) Pharmacokinetic Parameters for Healthy Adult Subjects on Day 5 After
Administration of DEXLANSOPRAZOLE
| Dose | Cmax | tmaxb | t1/2a | AUC24 | CL/F | Vz/F | ||||||||||||
| (mg) | (ng/mL) | (h) | (h) | (ng·h/mL) | (L/h) | |||||||||||||
| 30 | 658 (40%) (N=44) | 4.98 (0.98-7.98) (N=44) | 1.49 (N=43) | 3275 (47%) (N=43) | 11.4 (48%) (N=43) | 25.7 (49%) (N=43) | ||||||||||||
| 60 | 1397 (51%) (N=79) | 4 (1-12) (N=79) | 1.54 (N=73) | 6529 (60%) (N=73) | 11.6 (46%) (N=41) | 33.8 (89%) (N=41) | ||||||||||||
a Harmonic mean
b Median (min-max)
Dexlansoprazole is eliminated with a half-life of approximately 1 to 2 hours in healthy subjects (see Table 5) and in patients with symptomatic GERD. No accumulation of dexlansoprazole occurs after multiple, once daily doses of DEXLANSOPRAZOLE 30 mg or 60 mg. The formulation of DEXLANSOPRAZOLE utilizing Dual Delayed Release technology results in a dexlansoprazole plasma concentration-time profile with two distinct peaks; the first peak occurs 1 to 2 hours after administration, followed by a second peak within 4 to 5 hours (see Figure 1).
Figure 1- Mean Plasma Dexlansoprazole Concentration – Time Profile Following Oral Administration of 60 mg DEXLANSOPRAZOLE or 30 mg Lansoprazole Once Daily for 5 Days in Healthy Adult Subjects
Time (h)
0 4 8 12 16 20 24
0
200
400
600
800
1000
1200
DEXILANT 60 mg Lansoprazole 30 mg
Absorption:
After oral administration of DEXLANSOPRAZOLE 30 mg or 60 mg to healthy subjects, mean Cmax and AUC values of dexlansoprazole increased approximately dose proportionally (see Figure 2).
Figure 2- Mean Plasma Dexlansoprazole Concentration – Time Profile Following Oral Administration of DEXLANSOPRAZOLE on Day 5 in Healthy Adult Subjects
T im e (h ) 0 4 8 1 2 1 6 2 0 2 4
0
2 0 0
4 0 0
6 0 0
8 0 0
1 0 0 0
1 2 0 0 D E X IL A N T 3 0 m g
D E X IL A N T 6 0 m g
Distribution:
Plasma protein binding of dexlansoprazole ranged from 96.1% to 98.8% in healthy subjects and was
independent of concentration from 0.01 to 20 mcg/mL. The apparent volume of distribution (Vz/F) after multiple doses in symptomatic GERD patients was 40.3 L.
Metabolism:
Dexlansoprazole is extensively metabolized in the liver by oxidation, reduction, and subsequent formation of sulfate, glucuronide and glutathione conjugates to inactive metabolites. Oxidative metabolites are formed by the cytochrome P450 (CYP) enzyme system including hydroxylation mainly by CYP2C19, and oxidation to the sulfone by CYP3A4.
CYP2C19 is a polymorphic liver enzyme which exhibits three phenotypes in the metabolism of CYP2C19 substrates; extensive metabolizers (*1/*1), intermediate metabolizers (*1/mutant) and poor metabolizers (mutant/mutant). Systemic exposure of dexlansoprazole is generally higher in intermediate and poor metabolizers. Dexlansoprazole is the major circulating component in plasma, regardless of CYP2C19 metabolizer status. In CYP2C19 intermediate and extensive metabolizers, the major plasma metabolites are 5-hydroxy dexlansoprazole and its glucuronide conjugate, while in CYP2C19 poor metabolizers dexlansoprazole sulfone is the major plasma metabolite.
Elimination:
Following the administration of DEXLANSOPRAZOLE, no unchanged dexlansoprazole is excreted in urine. Following the administration of [14C]dexlansoprazole to 6 healthy male subjects, approximately 50.7% (standard deviation (SD): 9.0%) of the administered radioactivity was excreted in urine and 47.6% (SD: 7.3%) in the feces. Apparent clearance (CL/F) in healthy subjects was 11.4 to 11.6 L/h, respectively, after 5-days of 30 or 60 mg once daily administration.
Effect of Food:
DEXLANSOPRAZOLE can be taken without regard to food or the timing of food. In food-effect studies in healthy subjects receiving DEXLANSOPRAZOLE, increases in Cmax ranged from 12% to 55% and increases in AUC ranged from 9% to 37% under various fed conditions compared to fasting. However, no relevant differences with regard to intragastric pH were observed. An additional study showed that administration of 60 mg DEXLANSOPRAZOLE prior to consumption of breakfast, lunch, dinner or an evening snack did not have an effect on dexlansoprazole exposure, or a clinically relevant effect on 24-hour intragastric pH control.
Special Populations and Conditions
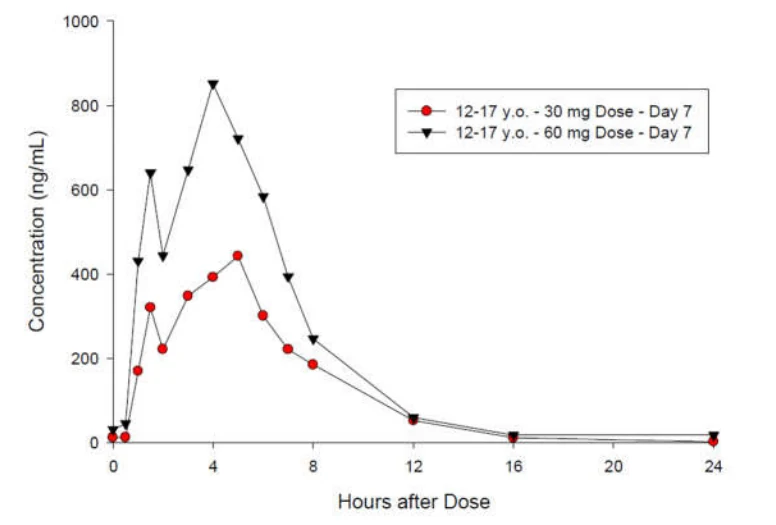
Pediatrics: In a study of 36 adolescents 12 to 17 years old with symptomatic GERD, dexlansoprazole pharmacokinetics (See Figure 3 and Table 6) were similar to those observed in healthy adults (See Figure 2 and Table 5). In adolescents, dexlansoprazole mean Cmax was 81% to 105% of the adult mean Cmax value, mean AUC was 78% to 88% of the adult mean AUC value, and mean CL/F was 112% to 132% of the adult mean CL/F value.
Table 6 - Mean (CV %) Pharmacokinetic Parameters in Adolescents 12 to 17 Years of Age with
Symptomatic GERD on Day 7 After Administration of DEXLANSOPRAZOLE once daily for 7 days
| Dose | Cmax | AUCτ | CL/F | ||||||||
| (mg) | (ng/mL) | (ng·h/mL) | (L/h) | ||||||||
30 (N=17) | 691 (53%) | 2886 (47%) | 12.8 (48%) | ||||||||
60 (N=18) | 1136 (51%) | 5120 (58%) | 15.3 (49%) | ||||||||
Note: area under the concentration-time curve during a dosing interval (AUCτ)
Figure 3 - Mean Dexlansoprazole Plasma Concentration – Time Profile Following Administration of 30 or 60 mg DEXLANSOPRAZOLE Capsules Once Daily for 7 Days in Adolescents 12 to 17 Years of Age with Symptomatic GERD
The pharmacokinetics of dexlansoprazole in patients under the age of 12 years have not been studied.
- Geriatrics: In a study of 12 male and 12 female healthy subjects who received a single oral dose of DEXLANSOPRAZOLE 60 mg, the terminal elimination half-life of dexlansoprazole was statistically significantly longer in geriatric subjects compared to younger subjects (2.23 and 1.5 hours, respectively). In addition, dexlansoprazole exhibited higher systemic exposure (AUC) in geriatric subjects (34.5% higher) than younger subjects. These differences were not clinically relevant. No dosage adjustment is necessary in geriatric patients. See 7 WARNINGS AND PRECAUTIONS and 4 DOSAGE AND ADMINISTRATION.
Sex: In a study of 12 male and 12 female healthy subjects who received a single oral dose of
DEXLANSOPRAZOLE 60 mg, females had higher systemic exposure (AUC) (42.8% higher) than males. No dosage adjustment is necessary in patients based on gender.
- Hepatic Insufficiency: In a study of 12 patients with moderately impaired hepatic function who received a single oral dose of DEXLANSOPRAZOLE 60 mg, plasma exposure (AUC) of bound and unbound dexlansoprazole in the hepatic impairment group was approximately 2 times greater compared to subjects with normal hepatic function. This difference in exposure was not due to a difference in protein binding between the two liver function groups. No adjustment for DEXLANSOPRAZOLE is necessary for patients with mild hepatic impairment (Child-Pugh Class A). DEXLANSOPRAZOLE 30 mg should be considered for patients with moderate hepatic impairment (Child-Pugh Class B). No studies have been conducted in patients with severe hepatic impairment (Child-Pugh Class C). See 7 WARNINGS AND PRECAUTIONS.
- Renal Insufficiency: Dexlansoprazole is extensively metabolized in the liver to inactive metabolites, and no parent drug is recovered in the urine following an oral dose of dexlansoprazole. Therefore, the pharmacokinetics of dexlansoprazole are not expected to be altered in patients with renal impairment, and no studies were conducted in subjects with renal impairment. See 7 WARNINGS AND PRECAUTIONS.
11 STORAGE, STABILITY AND DISPOSAL
Store at room temperature (15° to 30°C).
12 SPECIAL HANDLING INSTRUCTIONS
No special handling instructions are required for this product.
PART II: SCIENTIFIC INFORMATION
13 PHARMACEUTICAL INFORMATION
Drug Substance
Proper name: Dexlansoprazole
Chemical name: (+)-2-[(R)-{[3-methyl-4-(2,2,2-trifluoroethoxy)pyridin-2-yl] methyl} sulfinyl]-1H-benzimidazole
Molecular formula and molecular mass: C16H14F3N3O2S 369.36
Structural formula:
N
HN S
O N
CH3
O CF3
Physicochemical properties: Dexlansoprazole is a white to nearly white crystalline powder which melts with decomposition at 140°C. Dexlansoprazole is the R-enantiomer of lansoprazole (a racemic mixture of the R- and S-enantiomers).
Dexlansoprazole is freely soluble in dimethylformamide, methanol, dichloromethane, ethanol, and ethyl acetate; and soluble in acetonitrile; slightly soluble in ether; and very slightly soluble in water; and practically insoluble in hexane.
Dexlansoprazole is stable when exposed to light. Dexlansoprazole is more stable in neutral and alkaline conditions than acidic conditions.
14 CLINICAL TRIALS
14.1 Efficacy and Safety Studies
Healing of Erosive Esophagitis in Adult Patients
Table 7 - Summary of patient demographics for adult clinical trials in healing of erosive esophagitis
| Study # | Study design | Dosage, route of administration and duration | Study | Mean age (Range) | Sex | ||
| subjects | |||||||
| (n) | |||||||
| T-EE04-084 | Randomized, double-blind, active-controlled | DEXLANSOPRAZOLE: 60 mg QD, 90 mg QD, Oral Lansoprazole delayed release: 30 mg QD, Oral 4 or 8 weeks | 2038 | 47.5 (18 to 87 years) | Males and females | ||
| T-EE04-085 | Randomized, double-blind, active-controlled | DEXLANSOPRAZOLE: 60 mg QD, 90 mg QD, Oral Lansoprazole delayed release: 30 mg QD, Oral 4 or 8 weeks | 2054 | 47.9 (18 to 90 years) | Males and females |
Two multi-center, double-blind, active-controlled, randomized, 8-week studies were conducted in patients with endoscopically confirmed erosive esophagitis. Severity of the disease was classified based on the Los Angeles Classification Grading System (Grades A-D). Patients were randomized to one of the following three treatment groups: DEXLANSOPRAZOLE 60 mg daily, DEXLANSOPRAZOLE 90 mg daily or lansoprazole 30 mg daily. A total of 4092 patients were enrolled and ranged in age from 18 to 90 years (median age 48 years) with 54% male. Race was distributed as follows: 87% Caucasian, 5% Black and 8% other. Based on the Los Angeles Classification, 71% of patients had Grades A and B erosive esophagitis (mild) and 29% of patients had Grades C and D erosive esophagitis (moderate to severe) before treatment.
Maintenance of Healed Erosive Esophagitis in Adult Patients
Table 8- Summary of patient demographics for adult clinical trials in maintenance of healed erosive esophagitis
| Study # | Study design | Dosage, route of administration and duration | Study | Mean age (Range) | Sex | ||
| subjects | |||||||
| (n) | |||||||
| T-EE05-135 | Randomized, double-blind, placebo-controlled | DEXLANSOPRAZOLE: 30 mg QD, 60 mg QD, Oral Placebo QD, Oral 6 months | 445 | 49 (18 to
| Males and females | ||
A multi-center, double-blind, placebo-controlled, randomized study was conducted in patients who successfully completed a erosive esophagitis study and showed endoscopically confirmed healed erosive esophagitis. Maintenance of healing and symptom relief over a six-month period were evaluated with DEXLANSOPRAZOLE 30 mg or 60 mg once daily compared to placebo. A total of 445 patients were enrolled and ranged in age from 18 to 85 years (median age 49 years), with 52% female. Race was distributed as follows: 90% Caucasian, 5% Black and 5% other.
Symptomatic GERD in Adult Patients
Table 9- Summary of patient demographics for adult clinical trials in symptomatic non-erosive GERD
| Study # | Study design | Dosage, route of | Study | Mean age (Range) | Sex | ||||
| administration and | subjects | ||||||||
| duration | (n) | ||||||||
| T-GD05-137 | Randomized, double-blind, multicenter, placebo-controlled, parallel-group, 3 arm | DEXLANSOPRAZOLE: 30 mg QD, 60 mg QD, Oral Placebo QD, Oral 4 weeks | 947 | 48 (18 to
| Males and females | ||||
A multi-center, double-blind, placebo-controlled, randomized, 4-week study was conducted in patients with a diagnosis of symptomatic GERD made primarily by presentation of symptoms. These patients who identified heartburn as their primary symptom, had a history of heartburn for 6 months or longer, had heartburn on at least 4 of 7 days immediately prior to randomization and had no esophageal erosions as confirmed by endoscopy. However, patients with symptoms which were not acid-related may not have been excluded using these inclusion criteria. Patients were randomized to one of the following treatment groups: DEXLANSOPRAZOLE 30 mg daily, 60 mg daily, or placebo. A total of 947 patients were enrolled and ranged in age from 18 to 86 years (median age 48 years) with 71% female. Race was distributed as follows: 82% Caucasian, 14% Black and 4% other.
Healing of EE, Maintenance of Healed EE: Adolescents 12 to 17 Years of Age
Table 10- Summary of patient demographics for adolescent clinical trials in healing of erosive esophagitis and maintenance of healed erosive esophagitis
| Study # | Study design | Dosage, route of | Study subjects (n) | Mean | Sex | ||||
| administration and | age | ||||||||
| duration | (Range) | ||||||||
TAK- 390MR_207 | Healing: open-label, multicenter, multiple-dose, noncomparative Maintenance: randomized, double-blind, multicenter, multiple-dose, parallel-group, placebo-controlled | Healing (8 weeks): DEXLANSOPRAZOLE 60 mg QD, Oral Maintenance (16 weeks): DEXLANSOPRAZOLE 30 mg QD, Oral Placebo QD, Oral | Healing: 62 Maintenance: 51 | 15 (12 to 17) years | Males and females | ||||
In a multi-center, 24-week study, 62 adolescents 12 to 17 years of age with a documented history of GERD for at least 3 months and endoscopically-proven EE were treated with dexlansoprazole 60 mg capsule once daily, for 8 weeks (single-arm open-label healing phase), followed by a 16-week maintenance phase (randomized double-blind placebo-controlled). The median age was 15 years with males accounting for 61% of the patients. Based on the Los Angeles Classification Grading Scale, 96.8%
of the EE patients had mild EE (Grades A and B), and 3.2% of patients had moderate to severe EE (Grades C and D) before treatment.
Symptomatic Non-Erosive GERD: Adolescents 12 to 17 Years of Age
Table 11- Summary of patient demographics for adolescent clinical trials in symptomatic non-erosive
GERD
| Study # | Study design | Dosage, route of | Study | Mean age (Range) | Sex | ||||
| administration and | subjects | ||||||||
| duration | (n) | ||||||||
| TAK-390MR_206 | Open-label, multicenter, multiple-dose, noncomparative | DEXLANSOPRAZOLE: 60 mg QD, Oral 4 weeks | 104 | 15 (12 to
| Males and females | ||||
In a single-arm uncontrolled, open-label, multi-center study, 104 adolescents 12 to 17 years of age with symptomatic non-erosive GERD were treated with dexlansoprazole 30 mg capsule once daily, for 4 weeks. Patients had a documented history of GERD symptoms for at least 3 months prior to screening, reported heartburn on at least three out of seven days during screening, and no esophageal erosions as confirmed by endoscopy. Patients ranged in age from 12 to 17 years (median age 15 years) with females accounting for 70% of the patients.
14.2 Study Results
Healing of Erosive Esophagitis in Adult Patients
By the life-table method of analysis DEXLANSOPRAZOLE 60 mg healed 92.3% to 93.1% of patients versus 86.1% to 91.5% for lansoprazole 30 mg after 8 weeks of treatment. Non-inferiority was demonstrated in both studies. Statistical superiority was not established using log-rank tests.
The crude rate estimates considered patients who did not have endoscopically documented healed erosive esophagitis and who discontinued prematurely as not healed. Based on crude rate estimates, healing rates at Week 4 (secondary) or Week 8 (primary) were higher for DEXLANSOPRAZOLE than lansoprazole (Table 12). Treatment with DEXLANSOPRAZOLE 60 mg was non-inferior to lansoprazole 30 mg at Week 8 in both studies. Statistical superiority of DEXLANSOPRAZOLE 60 mg over lansoprazole 30 mg was established in the first study but was not replicated in the second study.
Table 12- Erosive Esophagitis Healing Rates in Adults – All Grades
| Study | Number of Patients (N) | Treatment Group (Daily) | Week 4 % Healed | Week 8 % Healed a | (95% CI) for the | p-value Week 8 | ||
| Treatment | ||||||||
| Difference | ||||||||
| (DEXLANSOPRAZOLE | ||||||||
| ||||||||
| Week 8 | ||||||||
| 1 | 639 | DEXLANSOPRAZOLE 60 mg | 66.2 | 85.3 | (2.17, 10.48) b | 0.004* | ||
| 656 | Lansoprazole 30 mg | 64.8 | 79.0 | |||||
| 2 | 657 | DEXLANSOPRAZOLE 60 mg | 69.7 | 86.9 | (-1.45, 6.14) b | 0.234 | ||
| 648 | Lansoprazole 30 mg | 65.4 | 84.6 | |||||
CI = Confidence interval
a Primary efficacy endpoint by the crude rate method of analysis
b Demonstrated non-inferiority to lansoprazole
*Statistically significant
The life-table healing rates at Week 8 for patients with moderate to severe erosive esophagitis were 88.9% and 74.5% for DEXLANSOPRAZOLE 60 mg and lansoprazole 30 mg, respectively, in the first study. The difference was statistically significant (p=0.011). In the second study, the Week 8 life-table healing rates were 87.6% and 87.7% for DEXLANSOPRAZOLE 60 mg and lansoprazole 30 mg, respectively, and were not statistically significantly different.
The crude healing rates at Week 8 for patients with moderate to severe erosive esophagitis are presented in Table 13.
Table 13- Healing Rates at Week 8 – Moderate to Severe Erosive Esophagitis in Adults
| Study | Number of | Treatment Group (Daily) | Week 8 | p-value | ||||||
| Patients (N) | % Healed a | Week 8 | ||||||||
| 1 | 182 | DEXLANSOPRAZOLE 60 mg | 79.7 | 0.002* | ||||||
| 200 | Lansoprazole 30 mg | 65.0 | ||||||||
| 2 | 194 | DEXLANSOPRAZOLE 60 mg | 77.8 | 0.768 | ||||||
| 190 | Lansoprazole 30 mg | 78.9 | ||||||||
a Healing rates are by the crude rate method of analysis
*Statistically significant
DEXLANSOPRAZOLE 90 mg was studied and did not provide additional clinical benefit over DEXLANSOPRAZOLE 60 mg.
Maintenance of Healed Erosive Esophagitis in Adult Patients
By the life-table method, DEXLANSOPRAZOLE 30 mg and 60 mg demonstrated statistically significantly higher rates of maintenance of healed erosive esophagitis (74.9% and 82.5%, respectively) than placebo (27.2%) at Month 6 (p<0.00001).
Based on crude rate estimates, 66.4% percent of patients treated with 30 mg or 60 mg of DEXLANSOPRAZOLE remained healed over the six-month time period versus 14.3% of placebo patients (p<0.00001) (Table 14).
Table 14- Maintenance Rates a of Healed EE in Adults at Month 6
| Number of Patients (N) b | Treatment Group (Daily) | Maintenance Rate | ||||||
| 125 | DEXLANSOPRAZOLE 30 mg | 66.4* | ||||||
| 119 | Placebo | 14.3 | ||||||
a Based on crude rate estimates, patients who did not have endoscopically documented relapse and prematurely discontinued were considered to have relapsed.
b Patients with at least one post baseline endoscopy
* Statistically significant vs. placebo
For patients with more severe grades of erosive esophagitis (Grades C or D) before healing, DEXLANSOPRAZOLE 30 mg and 60 mg also achieved statistically significantly higher 6-month maintenance rates than placebo by the life-table method. For the crude rate analysis, the trends in the results were similar to the life-table analysis.
DEXLANSOPRAZOLE 30 mg and 60 mg achieved statistically significantly (p<0.00001) greater percentages of 24-hour heartburn-free periods, and heartburn free nights during the study treatment period, compared to placebo (see Tables 15 and 16).
Table 15- Median Percentage of 24-Hour Heartburn-Free Periods of the Maintenance of Healed EE
Study in Adults
| Treatment Group (daily) | N | Heartburn-Free 24-hour Periods (Median %) | ||||||
| DEXLANSOPRAZOLE 30 mg | 132 | 96.1* | ||||||
| DEXLANSOPRAZOLE 60 mg | 147 | 90.9 | ||||||
| Placebo | 141 | 28.6 | ||||||
* Statistically significant vs. placebo (p<0.00001)
Table 16- Median Percentage of Nighttime Heartburn-Free Periods of the Maintenance of Healed EE
Study in Adults
| Treatment Group (daily) | N | Heartburn-Free Nights (Median %) | ||||||
| DEXLANSOPRAZOLE 30 mg | 132 | 98.9* | ||||||
| DEXLANSOPRAZOLE 60 mg | 147 | 96.2 | ||||||
| Placebo | 140 | 71.7 | ||||||
* Statistically significant vs. placebo (p<0.00001)
In a second study (N=451) of DEXLANSOPRAZOLE 60 mg and 90 mg versus placebo, DEXLANSOPRAZOLE 60 mg showed similar results to the first study in the maintenance of healed erosive esophagitis and heartburn relief. DEXLANSOPRAZOLE 90 mg did not provide additional clinical benefit over DEXLANSOPRAZOLE 60 mg.
Symptomatic GERD in Adult PatientsDEXLANSOPRAZOLE 30 mg provided statistically significantly greater percent of days with heartburn-free 24-hour periods and percent of nights without heartburn over placebo as assessed by daily diary over 4 weeks (Table 17). DEXLANSOPRAZOLE 60 mg was studied and provided no additional clinical benefit over DEXLANSOPRAZOLE 30 mg.
Table 17- Median Percentages of Heartburn Relief During the 4 Week Treatment Period of the
Symptomatic GERD Study in Adults
| N | Treatment Group | Heartburn-Free 24-Hour | Nights without Heartburn | ||||||
| (daily) | Periods (%) | (%) | |||||||
| 312 | DEXLANSOPRAZOLE 30 mg | 54.9* | 80.8* | ||||||
| 310 | Placebo | 18.5 | 51.7 | ||||||
* Statistically significant vs. placebo (p<0.00001)
A higher percentage of patients on DEXLANSOPRAZOLE 30 mg had heartburn-free 24-hour periods compared to placebo through 4 weeks of treatment.
Healing of EE, Maintenance of Healed EE: Adolescents 12 to 17 Years of Age
Among the 62 patients enrolled in the healing phase, 58 patients completed the 8-week treatment, with 51 (82.3% out of 62) patients achieving EE healing by week 8. This corresponds to 87.9% of the 58 patients who completed the 8-week treatment.
After the initial 8 weeks of treatment, 51 patients with endoscopically confirmed healed EE were randomized to receive DEXLANSOPRAZOLE 30 mg capsule or placebo once daily for an additional 16 weeks, in order to assess the maintenance of EE healing. A total of 38 patients completed the maintenance phase. Eighty-two percent (81.8%) of patients treated with DEXLANSOPRAZOLE 30 mg capsule remained healed over the four-month treatment period as confirmed by endoscopy. The rate was 58.3% in patients treated with placebo (see Table 18).
Table 18- Maintenance of Healed EE After 16 weeks in Adolescents 12 to 17 Years of Age
| N | Treatment Group (daily) | Maintenance Rate (%) | ||||||
| 22 | DEXLANSOPRAZOLE 30 mg | 81.8 | ||||||
| 24 | Placebo | 58.3 | ||||||
During the 16-week maintenance period, median percentage of 24-hour heartburn-free periods were 86.6% for those receiving DEXLANSOPRAZOLE 30 mg capsule compared to 68.1% for those receiving placebo.
Symptomatic Non-Erosive GERD: Adolescents 12 to 17 Years of Age
During the 4-week treatment period, the median percentage of 24-hour heartburn free periods was 47.3%.
Overall, the efficacy results for healing of EE, maintenance of healed EE, and symptomatic non-erosive GERD in adolescents 12 to 17 years of age as enrolled in the studies did not appear to be substantially different from those reported in adults.
15 MICROBIOLOGY
No microbiological information is required for this drug product.
16 NON-CLINICAL TOXICOLOGY
General Toxicology: Multi-dose Studies: A thirteen-week oral toxicity study was conducted in Wistar rats. Animals were administered 5, 15 or 50 mg/kg/day of dexlansoprazole or 50 mg/kg/day of lansoprazole. Pharmacologically related increases in stomach weight were observed for all doses of dexlansoprazole and lansoprazole. The only histological findings attributed to test article treatment were eosinophilia of chief cells in the stomach at 15 and 50 mg/kg/day of dexlansoprazole and 50 mg/kg/day of lansoprazole, and slight centrilobular hepatocyte hypertrophy in the liver at 50 mg/kg/day of dexlansoprazole and lansoprazole.
In a thirteen-week oral toxicity study in dogs, animals were administered 5, 15 or 50 mg/kg/day of dexlansoprazole or 50 mg/kg/day of lansoprazole. Systemic exposure to dexlansoprazole generally was higher in animals dosed with dexlansoprazole at 50 mg/kg/day than with the same dosage of lansoprazole. The effects of dexlansoprazole and lansoprazole administered at 50 mg/kg/day were essentially the same. Pharmacologically related increases in stomach weight were observed at 15 and 50 mg/kg/day dexlansoprazole and lansoprazole 50 mg/kg/day. The only histological findings attributed to test article treatment were parietal cell vacuolation and/or single cell necrosis and slight accumulation of bile in hepatocellular canaliculi.
The no-observed-adverse-effect-level (NOAEL) of dexlansoprazole was 15 mg/kg/day in rats and 5 mg/kg/day in dogs.
Carcinogenicity: Lansoprazole is a racemic mixture of R- and S-enantiomers. Following administration of lansoprazole in humans and animals, the major component circulating in plasma is dexlansoprazole, the R-enantiomer of lansoprazole. Therefore, the carcinogenic potential of dexlansoprazole was assessed using existing lansoprazole studies. In two 24-month carcinogenicity studies, Sprague-Dawley rats were treated orally with lansoprazole at doses of 5 to 150 mg/kg/day, about 1 to 40 times the exposure on a body surface (mg/m2) basis of a 50 kg person of average height (1.46 m2 BSA) given the recommended human dose of lansoprazole of 30 mg/day (22.2 mg/m2). Lansoprazole produced dose-related gastric ECL cell hyperplasia and ECL cell carcinoids in both male and female rats. See 10.2 Pharmacodynamics.
In rats, lansoprazole also increased the incidence of intestinal metaplasia of the gastric epithelium in both sexes. In male rats, lansoprazole produced a dose-related increase of testicular interstitial cell adenomas. The incidence of these adenomas in rats receiving doses of 15 to 150 mg/kg/day (4 to 40 times the recommended lansoprazole human dose based on BSA) exceeded the low background incidence (range = 1.4 to 10%) for this strain of rat. Testicular interstitial cell adenoma also occurred in 1 of 30 rats treated with 50 mg lansoprazole/kg/day (13 times the recommended lansoprazole human dose based on BSA) in a 1-year toxicity study.
In a 24-month carcinogenicity study, CD-1 mice were treated orally with lansoprazole doses of 15 mg to 600 mg/kg/day, 2 to 80 times the recommended human dose based on BSA. Lansoprazole produced a dose-related increased incidence of gastric ECL cell hyperplasia. Lansoprazole also induced a low, non-dose-related incidence of carcinoid tumors in the gastric mucosa in several dose groups (one female mouse in the 15 mg/kg/day group, one male mouse in the 150 mg/kg/day group, and 2 males and 1 female in the 300 mg/kg/day group). It also produced an increased incidence of liver tumors (hepatocellular adenoma plus carcinoma). The tumor incidences in male mice treated with 300 mg and 600 mg lansoprazole/kg/day (40 to 80 times the recommended lansoprazole human dose based on BSA) and female mice treated with 150 mg to 600 mg lansoprazole/kg/day (20 to 80 times the recommended human dose based on BSA) exceeded the ranges of background incidences in historical controls for this strain of mice. Lansoprazole treatment produced adenoma of rete testis in male mice receiving 75 to 600 mg/kg/day (10 to 80 times the recommended lansoprazole human dose based on BSA).
Genotoxicity: Dexlansoprazole was positive in the Ames test. In an in vitro chromosome aberration test using Chinese hamster lung cells, dexlansoprazole was judged positive (equivocal) because the percentage of affected cells increased slightly but did not reach the pre-set criteria for a positive response. Dexlansoprazole was negative in the in vivo mouse micronucleus test.
Reproductive and Developmental Toxicology: An embryo-fetal toxicity study conducted in pregnant rabbits at oral dexlansoprazole doses up to 30 mg/kg/day (approximately 9-fold the maximum recommended human dexlansoprazole dose [60 mg] based on BSA) showed that exposure increased with dosage, and there were no substantive differences in the toxic effects of dexlansoprazole and lansoprazole. Dams treated with both test articles experienced transient effects on food consumption, body weights and fecal volume. No adverse effects on reproductive parameters nor test article-related fetal abnormalities occurred with either test article. The incidence of unossified talus was increased at 30 mg/kg/day of dexlansoprazole and lansoprazole. The dexlansoprazole NOAEL for general toxicity in the dams was 3 mg/ kg/day. For reproductive toxicity, the NOAEL was greater than or equal to 30 mg/kg/day. For embryo-fetal development, the NOAEL was 10 mg/kg.
Reproduction studies performed in pregnant rats with oral lansoprazole at doses up to 150 mg/kg/day (40 times the recommended human dose based on BSA) and in pregnant rabbits at oral lansoprazole doses up to 30 mg/kg/day (16 times the recommended human dose based on BSA) revealed no evidence of impaired fertility or harm to the fetus due to lansoprazole.
Juvenile Animal Toxicity Data: In a juvenile rat study, adverse effects on bone growth and development and heart valves were observed at lansoprazole doses higher than the maximum recommended equivalent human dose.
An eight-week oral toxicity study with a four-week recovery phase was conducted in juvenile rats with lansoprazole administered from postnatal Day 7 (age equivalent to neonatal humans) through 62 (age equivalent to approximately 14 years in humans) at doses of 40 to 500 mg/kg/day.
Heart valve thickening occurred at a lansoprazole dose of 500 mg/kg/day (approximately three to five times the expected dexlansoprazole exposure based on AUC in pediatric patients less than 12 years of age). Heart valve thickening was not observed at the next lower dose (250 mg/kg/day) and below. The findings trended towards reversibility after a four-week drug-free recovery period.
No effects on heart valves were observed in a 13-week intravenous toxicity study of lansoprazole in adolescent rats (approximately 12 years human age equivalence) at systemic exposures similar to those achieved in the eight-week oral toxicity study in juvenile (neonatal) rats.
In the eight-week oral toxicity study of lansoprazole, doses equal to or greater than 100 mg/kg/day produced delayed growth, with impairment of weight gain observed as early as postnatal Day 10 (age equivalent to neonatal humans). At the end of treatment, the signs of impaired growth at 100 mg/kg/day and higher included reductions in body weight (14% to 44% compared to controls), absolute weight of multiple organs, femur weight, femur length and crown-rump length. Femoral growth plate thickness was reduced only in males and only at the 500 mg/kg/day dose. The effects related to delayed growth persisted through the end of the 4-week recovery period. Longer term data were not collected.
In a follow-up developmental toxicity study, juvenile rats (12 rats per dose group) were orally administered with 250 and/or 500 mg/kg/day lansoprazole for four or eight weeks starting on postnatal Day (PND) 7 (age equivalent to neonatal humans), PND 14 (age equivalent to approximately one year in humans), or PND 21 (age equivalent to approximately two years in humans).
Signs of toxicity (lower mean body weight gain and heart valve thickening) were observed in almost all dose groups of juvenile rats. Incidences of heart valve thickening were 2/12, 5/12 and 0/12, respectively, in juvenile rats dosed starting at ages 7, 14, and 21 day with 500 mg/kg/day lansoprazole for 4 weeks. Heart valve thickening in animals dosed with 500 mg/kg/days lansoprazole for eight weeks starting at PND 7, 14, and 21 were 2/12, 7/12, and 1/12, respectively.
Due to high incidence of mortality (9 of 24 males were found dead and 12 of 24 males were euthanized between PND 18 and PND 21) in the 500 mg/kg/day dose group starting at PND 14, dose level for this group was changed from 500 mg/kg/day to 250 mg/kg/day. Incidences of heart valve thickening in juvenile rats dosed with 250 mg/kg/day (approximately two times the expected dexlansoprazole exposure based on AUC in pediatric patients less than 12 years of age) starting at PND 14 were two (2/12) and one (1/11) for four weeks and eight weeks exposures, respectively. Incidences of the heart valve thickening were observed in almost all dose groups. Juvenile rats younger than PND 21 (age equivalent to approximately two years in humans) were more sensitive to the development of heart valve thickening.
The relevance of heart valve thickening in these studies to pediatric patients less than 12 years of age is unknown. These findings are not relevant for patients 12 years of age and older.