


Product Monograph - Omeprazole (Laboratoire Riva)
SUMMARY PRODUCT INFORMATION
Route of Administration | Dosage Form / Strength | Clinically Relevant Non-medicinal Ingredients |
| Oral | Delayed release tablet, 20 mg omeprazole | None For a complete listing see Dosage Forms, Composition and Packaging section. |
INDICATIONS AND CLINICAL USE
OMEPRAZOLE (omeprazole) tablets are indicated for the treatment of frequent heartburn. Frequent heartburn is heartburn that occurs 2 or more days a week.
OMEPRAZOLE tablets are not indicated for infrequent heartburn (i.e. one episode of heartburn a week or less) or immediate relief of heartburn.
CONTRAINDICATIONS
- Hypersensitivity to omeprazole, substituted benzimidazoles or any of the components of this medication (see DOSAGE FORMS, COMPOSITION AND PACKAGING).
- Co-administration with rilpivirine is contraindicated.
WARNINGS AND PRECAUTIONS
General
In the presence of any alarming symptoms (e.g., nausea, significant unintentional weight loss, recurrent vomiting, dysphagia, haematemesis, melena or anemia) and when gastric ulcer is suspected or present, malignancy should be excluded, as treatment may alleviate symptoms and delay diagnosis.
Concomitant administration with atazanavir and nelfinavir is not recommended (see DRUG INTERACTIONS).
Results from studies in healthy subjects have shown a pharmacokinetic/pharmacodynamic interaction between clopidogrel (300 mg loading dose/75 mg daily maintenance dose) and omeprazole (80 mg once daily, i.e. four times the recommended dose) resulting in decreased exposure to the active metabolite of clopidogrel by an average of 46% and resulting in decreased maximum inhibition of (ADP induced) platelet aggregation by an average of 16%. Based on these data, concomitant use of omeprazole and clopidogrel should be avoided (see DRUG INTERACTIONS).
Concomitant use of Proton Pump Inhibitors (PPIs) with Methotrexate
Literature suggests that concomitant use of PPIs with methotrexate (primarily at high dose) may elevate and prolong serum levels of methotrexate and/or its metabolite, possibly leading to methotrexate toxicities. A temporary withdrawal of the PPI may be considered in some patients receiving treatments with high dose methotrexate (see DRUG INTERACTIONS).
Patients should be advised to consult their doctor if:
- Their heartburn continues or worsens.
- They need to take omeprazole for more than 14 days or require more than 1 course of treatment within a 4-month period.
- They experience heartburn with lightheadedness, sweating or dizziness.
- They have chest pain or shoulder pain with shortness of breath, sweating, pain spreading to arms, neck or shoulders, or lightheadedness.
- They have frequent chest pain.
- They have frequent wheezing, particularly with heartburn.
- They have stomach pain.
Carcinogenesis and Mutagenesis
The rat carcinogenicity study (24 months) revealed a gradual development from gastric ECL-cell hyperplasia to carcinoids at the end of their normal life-span during administration with 14 - 140 mg/kg/day of omeprazole. No metastasis developed. No carcinoids developed during 18 months of high-dose treatment in mice (14 - 140 mg/kg/day). Similarly, administration of omeprazole up to 28 mg/kg/day in dogs for 7 years did not cause any carcinoids.
The gastric carcinoids in rats were related to sustained hypergastrinemia secondary to acid inhibition and not to omeprazole per se (see TOXICOLOGY). Similar observations have been made after administration of histamine H2-receptor blockers and also in partially fundectomized rats.
Short-term treatment and long-term treatment with omeprazole capsules in a limited number of patients for up to 6 years have not resulted in any significant pathological changes in gastric oxyntic endocrine cells.
Immune
Subacute cutaneous lupus erythematosus:
Subacute cutaneous lupus erythematosus (SCLE) has been reported with the use of PPIs. If lesions occur, especially in sun-exposed areas of the skin, and if accompanied by arthralgia, the patient should seek medical help promptly and the health care professional should consider stopping
OMEPRAZOLE. The occurrence of SCLE with previous PPI treatment may increase the risk of SCLE with other PPIs (see ADVERSE REACTIONS, Post-Market Adverse Drug Reactions).
Endocrine and Metabolism
Hypomagnesaemia, Hypokalemia and Hypocalcemia: The chronic use of PPIs may lead to hypomagnesaemia. Moreover, hypokalemia and hypocalcemia have been reported in the literature as accompanying electrolyte disorders.
Gastrointestinal
Pseudomembranous colitis has been reported with nearly all antibacterial agents, including clarithromycin and amoxicillin, and may range in severity from mild to life threatening. Therefore, it is important to consider this diagnosis in patients who present with diarrhea subsequent to the administration of antibacterial agents.
Treatment with antibacterial agents alters the normal flora of the colon and may permit overgrowth of Clostridia. Studies indicate that a toxin produced by Clostridium difficile is a primary cause of “antibiotic-associated colitis”.
After the diagnosis of pseudomembranous colitis has been established, therapeutic measures should be initiated. Mild cases of pseudomembranous colitis usually respond to discontinuation of the drug alone. In moderate to severe cases, consideration should be given to management with fluids and electrolytes, protein supplementation, and treatment with an antibacterial drug clinically effective against Clostridium difficile colitis.
Decreased gastric acidity due to any means, including any PPIs, increases gastric counts of bacteria normally present in the gastrointestinal tract. Treatment with PPIs may lead to a slightly increased risk of gastrointestinal infections such as Salmonella, Campylobacter and possibly Clostridium difficile.
Long-term use of OMEPRAZOLE is associated with an increased risk of fundic gland polyps especially beyond one year (see ADVERSE REACTIONS, Post-Market Adverse Drug Reactions). Most fundic gland polyps are asymptomatic. Use the lowest dose and shortest duration of PPI therapy appropriate to the condition being treated.
Special Populations
Pregnant Women: The safety of omeprazole in pregnancy has not been established. Omeprazole tablets should not be administered to pregnant women unless the expected benefits outweigh the potential risks.
Nursing Women: Omeprazole is secreted in breast milk. Omeprazole tablets should not be given to nursing mothers unless its use is considered essential.
Pediatrics (<18 years of age): The safety and effectiveness of omeprazole tablets in children have not yet been established. Omeprazole tablets should not be used in children under 18 years of age.
Geriatrics (>65 years of age): Information on the bioavailability of omeprazole 20 mg tablets in elderly patients is not currently available. However, based on data obtained from studies with intravenous (i.v.) administration of omeprazole and oral administration of omeprazole capsules, elderly subjects showed increased bioavailability (36%), reduced total plasma clearance (to 250 mL/min) and prolonged (50%) elimination of half-life (to 1.0 hour). The daily dose in elderly patients should, as a rule, not exceed 20 mg (see DOSAGE AND ADMINISTRATION).
Hepatic Impairment: Information on the bioavailability of omeprazole 20 mg tablets in patients with hepatic insufficiency is not currently available. However, based on data obtained from studies with i.v. administration of omeprazole and oral administration of omeprazole capsules, patients with impaired liver function showed a 75% increase in bioavailability, reduced total plasma clearance (to 67 mL/min) and a four-fold prolongation of the elimination half-life (to 2.8 hours). A dose of 20 mg omeprazole capsules given once daily to these patients for 4 weeks was well tolerated, with no accumulation of omeprazole or its metabolites. The daily dose in patients with severe liver disease should, as a rule, not exceed
20 mg (see DOSAGE AND ADMINISTRATION).
Renal Impairment: Information on the bioavailability of omeprazole 20 mg tablets in patients with renal insufficiency is not currently available. However, based on data obtained from studies with i.v. administration of omeprazole and oral administration of omeprazole capsules, the disposition of intact omeprazole is unchanged in patients with impaired renal function, and no dose adjustment is needed in these patients (see DOSAGE AND ADMINISTRATION).
Cyanocobalamin (Vitamin B12) Deficiency: The prolonged use of PPIs, may impair the absorption of protein-bound Vitamin B12 and may contribute to the development of cyanocobalamin (Vitamin B12) deficiency.
Musculoskeletal and Connective Tissue
Bone Fracture: Several published observational studies suggest that PPI therapy may be associated with an increased risk for osteoporosis-related fractures of the hip, wrist, or spine. The risk of fracture was increased in patients who received high-dose, defined as multiple daily doses, and long-term PPI therapy (a year or longer). Patients should use the lowest dose and shortest duration of PPI therapy appropriate to the condition being treated. Patients at risk for osteoporosis-related fractures should be managed according to established treatment guidelines (see DOSAGE AND ADMINISTRATION and ADVERSE REACTIONS).
ADVERSE REACTIONS
Adverse Drug Reaction Overview
Omeprazole is well tolerated. Most adverse reactions have been mild and transient, and have shown no consistent relationship with treatment.
Clinical Trial Adverse Drug Reactions
Because clinical trials are conducted under very specific conditions the adverse drug reaction rates observed in the clinical trials may not reflect the rates observed in practice and should not be compared to the rates in the clinical trials of another drug. Adverse drug reaction information from clinical trials is useful for identifying drug-related adverse events and for approximating rates.
Adverse events have been recorded during 6 placebo-controlled clinical investigations of OTC omeprazole involving 6,286 subjects who took omeprazole (3,146 on omeprazole 20 mg and 3,139 on omeprazole 10 mg) and 3,120 subjects who took placebo. The most commonly reported adverse events in the omeprazole 20 mg group were headache (3%), diarrhea (2%) and infection (2%). These incidences were not significantly greater than those observed in subjects treated with placebo.
Table 1. Most Common Adverse Events in OTC Subjects in Placebo-Controlled Studies
| COSTART Term | Omeprazole 20 mg (N=3,146) | Placebo (N=3,120) | |||||||
| N | % | N | % | ||||||
| Overall | 470 | 15% | 442 | 14% | |||||
| Headache | 102 | 3% | 109 | 3% | |||||
| Diarrhea | 54 | 2% | 56 | 2% | |||||
| Infection | 51 | 2% | 62 | 2% | |||||
| Nausea | 36 | 1% | 30 | 1% | |||||
| Pain Abdominal | 35 | 1% | 29 | 1% | |||||
| Flatulence | 22 | 1% | 14 | <1% | |||||
| Pain Back | 21 | 1% | 16 | 1% | |||||
| Vomiting | 19 | 1% | 18 | 1% | |||||
| Pharyngitis | 19 | 1% | 12 | <1% | |||||
| Flu Syndrome | 17 | 1% | 13 | <1% | |||||
| Rhinitis | 17 | 1% | 14 | <1% | |||||
| Dyspepsia | 16 | 1% | 9 | <1% | |||||
| Pain | 16 | 1% | 10 | <1% | |||||
The percentage of discontinuations due to adverse events was also similar for omeprazole-treated subjects (0.5%) compared to placebo-treated subjects (0.6%), and were primarily due to nausea, headache, vomiting, diarrhea and/or abdominal pain.
The incidence of serious adverse events (SAEs) was low: 0.2% for omeprazole 20 mg subjects and 0.1% for placebo subjects. No SAE reported by subjects receiving omeprazole 20 mg was considered to be possibly or probably related to study medication.
The following is a list of adverse events reported in clinical trials or reported from routine post marketing surveillance of short term and chronic use of omeprazole. Events are classified within body system categories. The following definitions of frequencies are used: common:
≥1/100; uncommon: ≥1/1,000 and <1/100, rare: <1/1,000 and very rare: <1/10,000.
Blood and Lymphatic System: Rare: leukopenia, thrombocytopenia, agranulocytosis and pancytopenia. Very rare: aplastic anemia and bone marrow suppression.
Cardiac: Very rare: serious arrhythmia (increased QT interval, torsade de pointes, ventricular fibrillation, ventricular tachycardia).
Central and Peripheral Nervous System: Common: headache. Uncommon: dizziness, paresthesia, somnolence, insomnia and vertigo. Rare: reversible mental confusion, agitation, aggression, depression and hallucination occurring predominantly in severely ill patients.
Ear and Labyrinth: Very rare: tinnitus, vertigo, hearing loss and ear pain.
Endocrine: Rare: gynaecomastia.
Eye: Very rare: eye pain, papilledema, optic atrophy.
Gastrointestinal: Common: diarrhea, constipation, abdominal pain, nausea/vomiting and flatulence. Rare: dry mouth, stomatitis, gastrointestinal candidiasis, microscopic colitis and pancreatitis (some fatal).
Hepatobiliary: Uncommon: increased liver enzyme levels. Rare: encephalopathy in patients with pre-existing severe liver disease, hepatocellular necrosis requiring liver transplantation, hepatitis with or without jaundice and hepatic failure.
Musculoskeletal and Connective Tissue: Rare: arthralgia, muscular weakness and myalgia.
Neoplasms Benign, Malignant and Unspecified (including cysts and polyps): Very rare: gastric polyps, gastric cancer and gastric carcinoids.
Renal and Urinary: Rare: glycosuria, haematuria and pyuria.
Reproductive System and Breast: Very rare: impotence, decreased fertility.
Skin and Subcutaneous Tissue: Uncommon: rash, dermatitis and/or pruritus, and urticaria. Rare: photosensitivity, erythema multiforme, Stevens-Johnsons syndrome, toxic epidermal necrolysis (TEN) and alopecia.
Other Adverse Events: Uncommon: malaise, hypersensitive reactions including urticaria. Rare: hypersensitive reactions including angioedema, fever, bronchospasm and interstitial nephritis and anaphylactic shock; increased sweating, peripheral edema, blurred vision, taste disturbances and hyponatremia.
Post-Market Adverse Drug Reactions
Gastrointestinal: Withdrawal of long-term PPI therapy can lead to aggravation of acid related symptoms and may result in rebound acid hypersecretion.
Musculoskeletal and Connective Tissue: Osteoporosis and osteoporosis-related fractures have been reported with multiple daily doses and long-term PPI therapy.
There have been post-marketing reports of subacute cutaneous lupus erythematosus (SCLE) (see WARNINGS, Immune).
There have been post-marketing reports of fundic gland polyps (PGPs) (See WARNINGS, Gastrointestinal).
DRUG INTERACTIONS
Overview
The gastric acid suppression during treatment with omeprazole and other PPIs might decrease or increase the absorption of drugs with gastric pH dependent absorption. Thus, it can be predicted that the absorption of drugs such as ketoconazole, itraconazole and erlotinib can decrease during omeprazole treatment, as it does during treatment with other acid secretion inhibitors or antacids.
Omeprazole is metabolized by the cytochrome P-450 system (CYP), mainly in the liver. The pharmacokinetics of the following drugs, which are also metabolized through the cytochrome
P-450 system, have been evaluated during concomitant use of omeprazole capsules in humans: aminopyrine, antipyrine, clopidogrel, diazepam, phenytoin, warfarin (or other vitamin K antagonists), cilostazol*, theophylline, voriconazole, digoxin, propranolol, metoprolol, lidocaine, quinidine, ethanol, piroxicam, diclofenac and naproxen.
Omeprazole inhibits CYP 2C19, the major omeprazole metabolizing enzyme, and is partially metabolized by CYP 3A4. Drugs known to inhibit CYP 2C19 or CYP 3A4 or both (such as clarithromycin and voriconazole) may lead to increased omeprazole serum levels by decreasing the rate of omeprazole’s metabolism. Drugs known to induce CYP 2C19 or CYP 3A4 or both (such as rifampin and St John’s Wort) may lead to decreased omeprazole serum levels by increasing omeprazole’s rate of metabolism.
As omeprazole is metabolized through CYP 2C19, it can alter the metabolism and prolong elimination of diazepam, warfarin (R-warfarin), phenytoin, and cilostazol*.
*not marketed in Canada
There is a modest increase in the absorption of digoxin when omeprazole is co-administered in daily doses of 20 mg or 40 mg. This increase may be clinically relevant in patients who have renal impairment or are especially susceptible to digoxin toxicity.
Drug-Drug Interactions
General
Results from a range of interaction studies with omeprazole vs. other drugs indicate that omeprazole, 20-40 mg given repeatedly, has no influence on other clinically relevant isoforms of CYP, as shown by the lack of metabolic interaction with substrates for CYP 1A2 (caffeine, phenacetin, theophylline), CYP 2C9 (S-warfarin), CYP 2D6 (metoprolol, propranolol), CYP 2E1 (ethanol), and CYP 3A (cyclosporin, estradiol, lidocaine, quinidine).
Aminopyrine and Antipyrine
After 14 days of administration of 60 mg omeprazole once daily, the clearance of aminopyrine was reduced by 19%; the clearance of antipyrine was reduced by 14%. After 14 days of administration of 30 mg once daily, no significant changes in clearance were noted.
Antacids
No interaction with antacids administered concomitantly with omeprazole (given as capsules) has been found.
Antibiotics
Clarithromycin
Clarithromycin is known to inhibit CYP 2C19 and CYP 3A4, which may lead to increased omeprazole serum levels by decreasing the rate of omeprazole’s metabolism.
Erythromycin
In vivo data suggests that omeprazole does not inhibit the metabolism of erythromycin; however, as erythromycin is an inhibitor of CYP3A4, there is a potential for an interaction in which metabolism of omeprazole is decreased, which may lead to an increase in serum levels of omeprazole.
Antifungal Drugs
Itraconazole and Ketoconazole
The absorption of some drugs might be altered due to the decreased intragastric acidity. Thus, it can be predicted that the absorption of itraconazole and ketoconazole will decrease during omeprazole treatment, as it does during treatment with other acid secretion inhibitors or antacids.
Voriconazole
Concomitant administration of omeprazole and a CYP 2C19 and CYP 3A4 inhibitor, voriconazole, resulted in more than doubling of the omeprazole exposure. However, a dose adjustment of omeprazole is not required.
Antiretroviral Drugs
Omeprazole, like other acid-reducing agents, has been reported to interact with some antiretroviral drugs. The clinical importance and the mechanisms behind these interactions are not always known. A change in gastric pH may change the absorption of the antiretroviral drug. Other possible interaction mechanisms are via CYP 2C19.
Rilpivirine
Co-administration is contraindicated due to significant decrease in rilpivirine exposure and loss of therapeutic effect (see CONTRAINDICATIONS).
Atazanavir, Nelfinavir and Saquinavir:
Reports indicate that omeprazole has a significant impact on atazanavir exposure, decreasing AUC, Cmax and Cmin by more than 70%. This interaction is only partially overcome by the addition of ritonavir to the atazanavir treatment regimen. Similarly, decreased serum levels of nelfinavir have also been reported when given together with omeprazole. Concomitant administration of omeprazole with atazanavir and nelfinavir is therefore not recommended (see WARNINGS AND PRECAUTIONS). For other antiretroviral drugs, such as saquinavir, elevated serum levels have been reported. Co-administration of saquinavir requires caution and monitoring, along with potential dose reduction of saquinavir, due to increased saquinavir exposure and thus the risk of saquinavir-related toxicities (see the INVIRASE Product Monograph). Concomitant administration of omeprazole (40 mg daily) with saquinavir/ritonavir (1000/100 mg twice daily) increased squinavir AUC by 82% and Cmax by 75%.
There are also some antiretroviral drugs were unchanged serum levels have been reported when given with omeprazole.
Cilostazol*
Omeprazole, given in doses of 40 mg to healthy subjects in a crossover study, increased Cmax and AUC for cilostazol by 18% and 26% respectively, and one of its metabolites, 3,4dihydrocilostazol, by 29% and 69% respectively.
*not marketed in Canada
Clopidogrel
Results from studies in healthy subjects have shown a pharmacokinetic/pharmacodynamic interaction between clopidogrel (300 mg loading dose/75 mg daily maintenance dose) and omeprazole (80 mg once daily, i.e. four times the recommended dose) resulting in decreased exposure to the active metabolite of clopidogrel by an average of 46%, and resulting in decreased maximum inhibition of (ADP induced) platelet aggregation by an average of 16%. It is, however, uncertain to what extent this interaction is clinically important. One prospective, randomized (but incomplete) study (in over 3,760 patients comparing placebo with omeprazole 20 mg in patients treated with clopidogrel and acetyl salicylic acid (ASA)) and non-randomized, post-hoc analyses of data from large, prospective, randomized clinical outcome studies (in over 47,000 patients) did not show any evidence of an increased risk for adverse cardiovascular outcome when clopidogrel and PPIs, including omeprazole, were given concomitantly.
Results from a number of observational studies are inconsistent with regard to increased risk or no increased risk for cardiovascular thromboembolic events when clopidogrel is given together with a PPI.
When clopidogrel was given together with a fixed dose combination of esomeprazole 20 mg + ASA 81 mg compared to clopidogrel alone in a study in healthy subjects there was a decreased exposure by almost 40% of the active metabolite of clopidogrel. However, the maximum levels of inhibition of (ADP induced) platelet aggregation in these subjects were the same in the clopidogrel and clopidogrel + the combined (esomeprazole + ASA) product groups, likely due to the concomitant administration of low dose ASA (see WARNINGS AND PRECAUTIONS).
Diazepam
As omeprazole is metabolized through CYP 2C19, it can alter the metabolism and prolong elimination of diazepam. Following repeated dosing with omeprazole 40 mg once daily, the clearance of diazepam was decreased by 54%. The corresponding decrease after omeprazole 20 mg was 26%.
Digoxin
The absorption of digoxin can increase during treatment with omeprazole and other drugs that reduce gastric acidity. Concomitant treatment with omeprazole (20 mg daily) and digoxin in 10 healthy subjects increased the bioavailability of digoxin by an average of 10% (up to 30% in 2 out of 10 subjects).
Ethanol
There was no significant effect on the pharmacokinetics of ethanol after treatment with omeprazole 20 mg.
Lidocaine
No interaction with a single i.v. dose of lidocaine or its active metabolite, MEGX, was found after one week pre-treatment with omeprazole 40 mg once daily. There were no interactions between omeprazole and lidocaine or MEGX concerning pharmacokinetic variables.
Methotrexate
Case reports, published population pharmacokinetic studies, and retrospective analyses suggest that concomitant administration of PPIs and methotrexate (primarily at high dose) may elevate and prolong serum levels of methotrexate and/or its metabolite hydroxymethotrexate. However, no formal drug interaction studies of methotrexate with PPIs have been conducted (see
WARNINGS AND PRECAUTIONS).
NSAIDs (e.g., Piroxicam, Diclofenac and Naproxen)
There were no significant effects on the steady state pharmacokinetics of piroxicam, diclofenac, and naproxen following repeated dosing with omeprazole 20 mg in healthy volunteers.
Phenytoin
As omeprazole is metabolized through CYP 2C19, it can alter the metabolism and prolong elimination of phenytoin. Following three weeks of treatment with omeprazole 20 mg once daily, the steady state plasma levels of phenytoin in epileptic patients already receiving concomitant phenytoin treatment were not significantly affected. Urinary excretion of phenytoin and its main metabolite were also unchanged.
After single i.v. and oral doses of omeprazole capsules 40 mg in young, healthy volunteers, the clearance of phenytoin was decreased by 15-20%, and half-life was prolonged by 20-30%. Following repeated dosing with omeprazole 40 mg once daily, the elimination half-life of phenytoin was increased by 27%. Thus, there appears to be a dose-dependent inhibition of elimination of phenytoin by omeprazole.
Patients receiving phenytoin should be monitored to determine if it is necessary to adjust the dosage of these drugs when taken concomitantly with omeprazole.
Propranolol and Metoprolol
No effects on propranolol kinetics were observed in a steady state trial with 20 mg of omeprazole daily. Similarly, no effects on steady state plasma levels of metoprolol were observed after concomitant treatment with 40 mg omeprazole daily.
Quinidine
After one week of omeprazole 40 mg once daily, no effect was observed on the kinetics or pharmacodynamics of quinidine.
Tacrolimus
Although no clinical studies have been undertaken, there is a possibility that the concomitant administration of omeprazole and tacrolimus may increase serum levels of tacrolimus.
Theophylline
No effects on oral or i.v. theophylline kinetics have been observed after repeated once-daily doses of 40 mg omeprazole.
Warfarin (or other Vitamin K antagonists)
As omeprazole is metabolized through CYP 2C19, it can alter the metabolism and prolong elimination of warfarin (R-warfarin). Concomitant administration of omeprazole 20 mg in healthy subjects had no effect on plasma concentrations of the (S)-enantiomer of warfarin, but caused a slight, though statistically significant increase (12%) in the less potent (R)-enantiomer concentrations. A small but statistically significant increase (11%) in the anticoagulant effect of warfarin was also seen. In patients receiving warfarin or other vitamin K antagonists, monitoring of INR (International Normalised Ratio) is recommended and a reduction of the warfarin (or other vitamin K antagonist) dose may be necessary. Concomitant treatment with omeprazole 20 mg daily did not change coagulation time in patients on continuous treatment with warfarin.
Other Interactions
As demonstrated with other PPIs, prolonged use may impair the absorption of protein-bound Vitamin B12 and may contribute to the development of Vitamin B12 deficiency.
Drug-Food Interactions
No interaction with food after repeated dosing of omeprazole tablets has been found.
Drug-Herb Interactions
Drugs known to induce CYP 2C19 or CYP 3A4 or both, such as St John’s Wort (Hypericum performatum) may lead to decreased omeprazole serum levels by increasing omeprazole’s rate of metabolism.
Drug-Laboratory Interactions
During treatment with antisecretory drugs, serum gastrin increases in response to the decreased acid secretion. Also chromogranin A (CgA) increases due to decreased gastric acidity. The increased CgA level may interfere with investigations for neuroendocrine tumours. Literature reports indicate that PPI treatment should be stopped 5 to 14 days before CgA measurement. Measurements should be repeated if levels have not normalized by this time.
DOSAGE AND ADMINISTRATION
Patients should use the lowest dose and shortest duration of PPI therapy appropriate to the condition being treated.
The recommended dose of OMEPRAZOLE (omeprazole) for adults 18 years and older is 1 tablet given once daily for 14 days for the treatment of frequent heartburn (i.e. for heartburn that occurs more than 2 days a week). The maximum dose is 1 tablet in a 24-hour period. Symptom relief should be rapid. If symptom control is not achieved after 2 weeks, further investigation is recommended.
The tablets should be swallowed whole with a glass of water.
A 14-day course of therapy may be repeated every 4 months.
Patients with Renal Impairment: No dose adjustment is required (see WARNINGS AND PRECAUTIONS).
Patients with Hepatic Impairment: No dose adjustment is required. The daily dose should not exceed 20 mg (see WARNINGS AND PRECAUTIONS).
Geriatrics (>65 years of age): No dose adjustment is required. The daily dose should not exceed
20 mg (see WARNINGS AND PRECAUTIONS).
Missed Dose
. If you miss a dose of OMEPRAZOLE and remember within 12 hours, take it as soon as possible. Then go back to your regular schedule. However, if more than 12 hours have passed when you remember, do not take the missed tablet. Do not double the dose. Just take your next dose on time.
OVERDOSAGE
Rare reports have been received of overdosage with omeprazole. Single oral doses of up to 400 mg of omeprazole capsules have not resulted in any severe symptoms, and no specific treatment has been needed. One case report described that a single oral dose (560 mg) of omeprazole was associated with moderate increase of white blood cells, generalised malaise, nausea, vomiting, apathy, confusion, drowsiness, moderate headache, flatulence and abdominal pain. As in all cases where overdosing is suspected, treatment should be supportive and symptomatic. Any unabsorbed material should be removed from the gastrointestinal tract, and the patient should be carefully monitored.
The oral LD50 of omeprazole in male and female rats and mice was greater than 4,000 mg/kg. In dogs, the only sign of acute toxicity was vomiting, which occurred at doses of approximately 600 mg/kg (see TOXICOLOGY).
If you think you have taken too much OMEPRAZOLE, contact your healthcare professional, hospital emergency department or regional Poison Control Centre immediately, even if there are no symptoms.
ACTION AND CLINICAL PHARMACOLOGY
Mechanism of Action
Omeprazole inhibits the gastric enzyme H+/K+-ATPase (the proton pump) which catalyzes the exchange of H+ and K+. Omeprazole is effective in the inhibition of both basal acid secretion and stimulated acid secretion. The inhibition is dose-dependent. Daily oral doses of omeprazole 20 mg and higher showed a consistent and effective acid control.
Pharmacodynamics
Information from clinical trials in patients with duodenal ulcers in remission indicate that omeprazole 20 mg tablets demonstrate the same inhibition of stimulated acid secretion and similar effect on 24-hour intragastric pH as omeprazole 20 mg capsules. The mean decrease in peak acid output after pentagastrin stimulation was approximately 70%, after 5 days of dosing with omeprazole 20 mg tablet once daily. These data support the conclusion that omeprazole 20 mg tablet and capsule can be used with equivalent efficacy in the treatment of conditions where a reduction of gastric acid secretion is required.
Pharmacokinetics
Summary of Omeprazole Pharmacokinetic Parameters in Healthy Male Volunteers
Single Dose Arithmetic Mean | Cmax (ng/mL) | Tmax§ (h) | t½ (h) | AUCI (ng·h/mL) |
| Fasted | 542.1 | 2.5 | 1.1 | 920.7 |
| Fed | 670.4 | 6 | 1.4 | 2266.8 |
§ Expressed as the median
Absorption: Omeprazole tablets are absorbed rapidly. Food has no effect on the bioavailability of the tablet. Peak plasma levels occur on average within 2 hours. The 20 mg tablet and the 20 mg capsule are not bioequivalent in terms of plasma omeprazole AUC, Cmax and Tmax. Omeprazole 20 mg tablets demonstrate, after repeated dosing, increased plasma omeprazole AUC (18%) and maximum concentration (41%) in comparison to omeprazole 20 mg given as capsules.
The omeprazole capsule (as a multiple unit formulation) is usually emptied gradually from the stomach into the intestine. In contrast to the capsule, the tablet (as a single unit formulation) will enter the intestine and dissolve as one unit. Consequently, the absorption and first pass metabolism of the tablet take place only during a very limited period. This may be one of the reasons for the difference observed in the pharmacokinetic variables of the two formulations.
The antisecretory effect of omeprazole is directly proportional to the AUC; it is not dependent on the plasma concentration at any given time. Omeprazole is 95% bound to plasma proteins.
Metabolism and Excretion: Omeprazole undergoes first pass metabolism by the cytochrome P450 system, mainly in the liver, through CYP 2C19 and CYP 3A4. The CYP 2C19 isozyme, which is involved in the metabolism of all available PPIs, exhibits polymorphism. Approximately 3% of the Caucasian population and 15-20% of Asian populations lack a functional CYP 2C19 enzyme and are called poor metabolisers.
Following i.v. administration and oral administration (capsules) of omeprazole, 80% of the dose is recovered as urinary metabolites. The remaining 20% is excreted in the feces.
Special Populations and Conditions
Geriatrics: Elderly subjects showed a 36% increase in bioavailability, reduced total plasma clearance and reduced urinary excretion of metabolites. Elimination half-life was also prolonged by 50%. The mean urinary excretion of metabolites was 68% of the dose. These changes are consistent with reduction in pre-systemic and systemic elimination, typical in the elderly. The daily dose should, as a rule, not exceed 20 mg in this patient group (see WARNINGS AND PRECAUTIONS).
Hepatic Impairment: Patients with impaired liver function showed a 75% increase in bioavailability, reduced total plasma clearance, and a four-fold prolongation of the elimination half-life. Dosage for patients with liver cirrhosis and other liver dysfunction should, as a rule, not exceed 20 mg daily (see WARNINGS AND PRECAUTIONS).
Renal Impairment: The pharmacokinetics of omeprazole in patients with impaired renal function was virtually the same as in healthy subjects.
STORAGE AND STABILITY
OMEPRAZOLE (omeprazole) tablets are moisture sensitive and are therefore provided in 14 count blister packages. Store between 15 and 30ºC. Protect from moisture.
DOSAGE FORMS, COMPOSITION AND PACKAGING
OMEPRAZOLE 20 mg delayed release tablets are red-brown, circular, biconvex, enteric coated tablets, printed “OM 20” on one side and plain on the other side.
Each 20 mg tablet contains 20.6 mg of omeprazole magnesium and the following non-medicinal ingredients: Mannitol, microcrystalline cellulose, sodium starch glycolate, hydroxypropyl methylcellulose, talc, sodium stearyl fumarate, methacrylic acid copolymer, polyethylene glycol, titanium dioxide, iron oxide (red & yellow). The imprinting ink consists of shellac, isopropyl alcohol, iron oxide black, N-butyl alcohol, propylene glycol, ammonium hydroxide.
OMEPRAZOLE tablets are provided in 14-tablet blister packages.
PART II: SCIENTIFIC INFORMATION
PHARMACEUTICAL INFORMATION
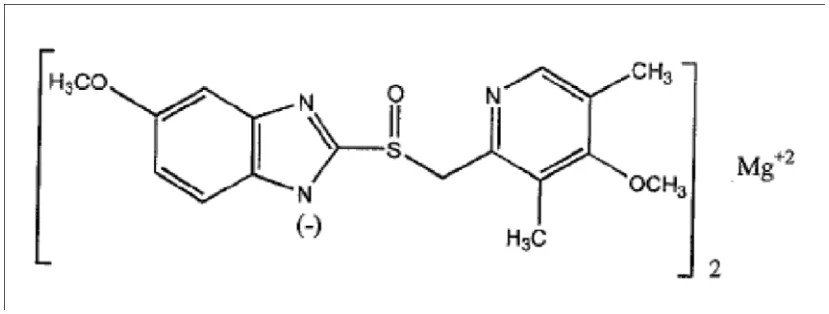
| Drug Substance | |
| Proper Name | Omeprazole magnesium |
| Chemical Name | Di (5-methoxy-2-{[(4-methoxy-3,5-dimethyl-2- pyridinyl)methyl]-sulfinyl}-1H-benzimidazole) magnesium |
| Molecular Formula | C34H36N6O6S2Mg |
| Molecular Weight | 713.1 g/mol (anhydrous basis) |
| Structural Formula | |
| Physicochemical Properties | Omeprazole magnesium is a white to off-white crystalline powder, containing between 2 and 4 waters of hydration. The solubility in water is 0.25 g/L, and the solubility in methanol is 10 g/L. Freely soluble in N,N Dimethyl formamide. The pKa of the benzimidazole (omeprazole base) is 8.8, and that of the pyridinium ion, 4.0. |
CLINICAL TRIALS
Heartburn
The prevention of frequent heartburn by omeprazole has been examined in two pivotal randomized, double-blind, placebo-controlled trials conducted in 2,086 subjects with heartburn 2 or more days per week. With consecutive daily dosing for 14 days, omeprazole treated subjects had a significantly greater percentage of heartburn free days than did placebo treated patients (64.4% vs. 39.4%; p<0.001, Study 1 and 67.8% vs. 37.9%; p<0.001, Study 2). Omeprazole-treated subjects had a greater percentage of nights with no nocturnal heartburn symptoms (84.7% vs. 74.5%; p≤0.05, Study 1 and 86.1% vs. 75.4%; p≤0.05, Study 2). Consecutive daily dosing with omeprazole also resulted in a greater percentage of days with no more than mild heartburn vs. placebo. For all 14-day outcomes, omeprazole provided significantly greater protection against heartburn than placebo in both studies.
 |
Comparative Bioavailability Studies
A double blind, randomised, single-dose, two-treatment, four-period, two-sequence, fully replicated crossover, comparative oral bioavailability study of OMEPRAZOLE 20 mg tablets (Laboratoire Riva Inc.) and Losec® (omeprazole magnesium) Delayed Release Tablets 20 mg was conducted in thirty one (31) healthy, adult, Asian male subjects under fasting conditions.
Omeprazole (1 X 20 mg) From measured data Geometric Mean Arithmetic Mean (CV %) | ||||
|---|---|---|---|---|
| Parameter | Test* | Reference† | % Ratio of Geometric Means | 90% Confidence Interval |
AUCT (ng.h / mL) | 907.0 1487.1 (115.8%)## | 953.4 1518.5 (112.8%)## | 95.1 | 89.4-101.3% |
AUCI (ng.h / mL) | 920.7 1500.5 (115.3%)## | 966.6 1566.0 (111.1 %) # | 95.2 | 89.5–101.4% |
Cmax (ng / mL) | 442.6 542.1 (64.5%)## | 481.1 580.5 (61.6%)## | 92.0 | 84.3-100.4% |
| Tmax§ (h) | 2.5 (1.3 – 5.5) ## | 2.7 (1.3 – 10.0) ## | ||
| T½€ (h) | 1.1 (64.0%)## | 1.2 (61.4%) # | ||
#n=60 and ## n=62.
* Omeprazole 20 mg tablets – Manufactured by: Laboratoire Riva Inc.
† Pr LOSEC® (Omeprazole Magnesium Delayed Release Tablets 20 mg) – Manufactured By: AstraZeneca Canada Inc., Canada, were purchased in Canada.
§ Expressed as the median (range) only
€ Expressed as the arithmetic mean (CV%) only
A double blind, randomised, single-dose, two-treatment, four-period, two-sequence, fully replicated crossover, comparative oral bioavailability study of OMEPRAZOLE 20 mg tablets (Laboratoire Riva Inc.) and Losec® (omeprazole magnesium) Delayed Release Tablets 20 mg was conducted in twenty seven (27) healthy, adult, Asian male subjects under fed conditions.
Omeprazole (1 X 20 mg) From measured data Geometric Mean Arithmetic Mean (CV %) | ||||
|---|---|---|---|---|
| Parameter | Test* | Reference† | % Ratio of Geometric Means | 90% Confidence Interval |
AUCT (ng.h / mL) | 1124.3 2007.7 (108.9%)# | 1076.0 2096.9 (115.5%)# | 104.5 | 87.9-124.2% |
AUCI ### (ng.h / mL) | 1347.0 2266.8 (99.7%)### | 1377.1 2383.4 (104.0%)### | 97.8 | 88.7–107.9% |
Cmax (ng / mL) | 511.9 670.4 (67.2%)# | 529.6 707.5 (65.6%)# | 96.6 | 81.9-114.0% |
| Tmax§(h) | 6 (3 – 22) # | 6 (3 – 22) ## | ||
| T½€ (h) | 1.4 (80.4%)### | 1.4 (82.2%)### | ||
#n=54, ##n=53 and ###n=48.
* Omeprazole 20 mg tablets – Manufactured by: Laboratoire Riva Inc.
† Pr LOSEC® (Omeprazole Magnesium Delayed Release Tablets 20 mg) – Manufactured By: AstraZeneca Canada Inc., Canada, were purchased in Canada.
§ Expressed as median (range) only
€ Expressed as the arithmetic mean (CV %) only
DETAILED PHARMACOLOGY
Animal Pharmacology
Pharmacodynamics
Omeprazole differs from existing inhibitors of gastric acid secretion such as histamine H2receptor antagonists and anticholinergic agents in its ability to directly inhibit the gastric H+/K+ATPase. This enzyme has been identified as the proton pump of the parietal cell.
Omeprazole had a long duration of action in all species studied. Repeated daily doses resulted in a progressive increase in the antisecretory effect during the first 3-5 days of administration. In dogs, a dose of 0.5 μmol/kg (given as enteric coated granules) inhibited histamine-stimulated gastric acid secretion by about 20% when measured 24 hours after the first dose, and by 60-65% when measured 24 hours after dosing at steady state. Once steady state conditions were reached (after 3-5 days), acid inhibition remained unchanged, as established in dogs treated for periods of up to one year.
Acid secretion recovers after discontinuation of long-term treatment at the same rate as after a single dose of omeprazole, in parallel with the recovery of H+/K+-ATPase activity in the oxyntic mucosa. Whether this recovery reflects de novo synthesis of the H+/K+-ATPase molecules or the dissociation of the inhibitor from the enzyme has not yet been established.
Due to the potency and long duration of action of omeprazole, repeated administrations of high doses in the rat resulted in a marked decrease of acid secretion and a secondary hypergastrinemia and hyperplasia of G-cells. In rats, administration of omeprazole 14-140 mg/kg/day resulted in plasma gastrin levels of 1,000-3,000 pg/mL as compared to 150-200 pg/mL in controls. In dogs, high doses of omeprazole (28 mg/kg/day) produced marked hypergastrinemia (1,0002,000 pg/mL after food intake), as compared to 100-300 pg/mL in controls. However, no hyperplasia of G-cells was evident in this species.
Secondary Pharmacological Effects
Mean arterial blood pressure and heart rate in the anesthetized dog were not affected by omeprazole under various challenges. Circulatory and respiratory functions in the dog were not affected by omeprazole, either at rest or during exercise. Omeprazole had no anticholinergic and no antihistamine (H2-receptor) activity. In the rat, no effect on basal locomotor activity or on exploratory activity was recorded, suggesting that omeprazole is devoid of sedative or neuroleptic effects.
Other Interactions
Omeprazole interacts with cytochrome P-450 in the rat liver. Omeprazole prolonged hexobarbital sleeping time by 12%.
Pharmacokinetics
Absorption and Distribution
Omeprazole is degraded rapidly in acidic gastric juice (rat and dog studies). Absorption is rapid. Peak plasma levels were found within 20 minutes and 1 hour after intra-duodenal and oral administration, respectively, in the dog. The drug has a low oral bioavailability, 5% in unstarved rats and 15-20% in starved male and female rats, if the drug is not protected by an enteric coating. The intra-duodenal bioavailability is approximately 70% and the oral bioavailability is approximately 15% in the dog. After absorption, omeprazole is rapidly distributed to extravascular sites and about 95% is bound to plasma proteins. The distribution of 14C-labelled omeprazole in the mouse was investigated by autoradiography. Radioactivity was initially found in the blood and most organs. Sixteen hours after administration, the drug was confined predominantly to the stomach wall. At 48 hours, the radioactivity was eliminated.
Penetration of omeprazole and/or its metabolites across the blood-brain and placental barriers was low.
Metabolism and Excretion
Omeprazole was extensively metabolized in all species studied. In rats and dogs approximately 20-30% of the dose was excreted as urinary metabolites and the remainder by biliary excretion as metabolites in the feces. Elimination was virtually complete within 72 hours. Identifiable metabolites constituted about 50% (rat) and 70% (dog) of the total metabolite excretion in 24 hours, and about 12% of the given dose in both species.
A study in lactating rats showed that omeprazole is excreted in breast milk. The concentration in the milk at 3-5 hours post dose was 100-200 times lower than the plasma concentration. A study on the administration of oral omeprazole during the third trimester of pregnancy and lactation (20 mg/day) showed that peak omeprazole concentrations in breast milk (58 nM, 3 h after ingestion) were less than 7% of the peak serum concentration (950 nM at 4 h), indicating minimal secretion.
Human Pharmacology
Pharmacodynamics
In both normal volunteers and hypersecretors, omeprazole inhibited basal nocturnal and daytime acid secretion as well as meal-, histamine-, and pentagastrin-stimulated secretion (omeprazole capsule data).
Table 2. Percentage Inhibition of Mean Acid Output After Single Oral Doses of Omeprazole
| Stimulus | Type of Subjects | Omeprazole Dose (mg) | Time After Dose (h) | |
| 20 | 80 | |||
| Basal | Hsu* | 33% | 1-4 | |
| Basal-Nocturnal | DU (rem)** | 49% | 15-24 | |
| Sham Feeding | HSu | 23% | 1.5-3.5 | |
| Betazol | HSu | 38% | 1-4 | |
| Pentagastrin | HSu | 36% | 1-4 | |
| Basal | ZES*** | 97% | 2-3 | |
* Healthy subject, **Duodenal ulcer in remission, ***Zollinger-Ellison syndrome
Repeated dosing with omeprazole capsule 20 mg once daily provided rapid inhibition of gastric acid secretion, with the maximum effect achieved within the first 4 days of treatment.
Information from clinical trials in patients with duodenal ulcers in remission indicates that omeprazole 20 mg tablets demonstrate the same inhibition of stimulated acid secretion and similar effect on 24-hour intragastric pH as omeprazole 20 mg capsules (mean proportion of time with pH >3 for capsule: 50.7%; for tablet: 57.35%). The mean decrease in peak acid output after pentagastrin stimulation was approximately 70%, after 5 days of dosing with omeprazole 20 mg tablet once daily.
Other Pharmacodynamic Effects
The effect of omeprazole on various organ systems has been investigated (data taken from clinical studies using omeprazole capsules). No clinically significant effects attributable to the drug could be found for the following parameters: Endocrine: plasma levels of insulin, Cpeptide, glucagon, parathyroid hormone, thyroid hormones or sex hormones, basal levels of cortisol; Cardiovascular: blood pressure, heart rate, electrocardiogram; Renal: renal handling of acid and electrolytes; Hepatic: liver enzymes. However, in some patients receiving omeprazole, elevated concentrations of alkaline phosphatase, S-AST and S-ALT have been reported (see
ADVERSE REACTIONS).
No clinically significant central nervous system effects have been recorded.
No clinically significant effects on other organ systems have been noted.
Omeprazole has no effect on acetylcholine or H2-receptors.
Pharmacokinetics
Omeprazole tablets are absorbed rapidly. Peak plasma levels occur on average within 2 hours. The 20 mg tablet and the 20 mg capsule are not bioequivalent in terms of plasma omeprazole AUC (geometric ratio and 90% confidence interval: 1.18, 1.06-1.30), Cmax (1.41, 1.24-1.60) and Tmax. Omeprazole 20 mg tablets demonstrate, after repeated dosing, increased plasma omeprazole AUC (18%) and maximum concentration (41%) in comparison to omeprazole 20 mg given as capsules.
The omeprazole capsule (as a multiple unit formulation) is usually emptied gradually from the stomach into the intestine. In contrast to the capsule, the tablet (as a single unit formulation) will enter the intestine and dissolve as one unit. Consequently, the absorption and first pass metabolism of the tablet take place during a very limited period. This may be one of the reasons for the difference observed in the pharmacokinetic variables of the two formulations.
The antisecretory effect of omeprazole is directly proportional to the AUC, and thus it is not dependent on the plasma concentration at any given time. Omeprazole is 95% bound to plasma proteins.
Omeprazole undergoes first pass metabolism, and is completely metabolized by the cytochrome P-450 system (CYP), mainly in the liver. The major part of its metabolism is dependent upon the polymorphically expressed, specific isoform, CYP 2C19 (S-mephenytoin hydroxylase). The remaining part is dependent on another specific isoform, CYP 3A4, responsible for the formation of omeprazole sulphone. As a consequence of high affinity of omeprazole to CYP 2C19, there is a potential for competitive inhibition and metabolic drug-drug interactions with other substrates for CYP 2C19. However, due to low affinity to CYP 3A4, omeprazole has no potential to inhibit the metabolism of other CYP 3A4 substrates.
The parameters below reflect mainly the pharmacokinetics in individuals with a functional CYP 2C19 enzyme, extensive metabolisers.
Total plasma clearance is about 30-40 L/h after a single dose. The plasma elimination half-life of omeprazole is usually shorter than one hour both after single and repeated oral once-daily dosing. The AUC of omeprazole increases with repeated administration. This increase is dosedependent and results in a non-linear dose-AUC relationship after repeated administration. This time- and dose-dependency is due to a decrease of first pass metabolism and systemic clearance probably caused by an inhibition of the CYP 2C19 enzyme by omeprazole and/or its metabolites (e.g., the sulphone). Omeprazole is completely eliminated from plasma between doses with no tendency for accumulation during once-daily administration.
Poor metabolisers: Approximately 3% of the Caucasian population and 15-20% of Asian populations lack a functional CYP 2C19 enzyme and are called poor metabolisers. In such individuals the metabolism of omeprazole is expected to be catalysed by CYP 3A4. After repeated once-daily administration of 20 mg omeprazole, the mean AUC was 5 to 10 times higher in poor metabolisers than in subjects having a functional CYP 2C19 enzyme (extensive metabolisers). Mean peak plasma concentrations were also higher, by 3 to 5 times. However, these findings have no implication on dosing of omeprazole.
Following i.v. administration and oral administration (capsules) of omeprazole, 80% of the dose is recovered as urinary metabolites. The remaining 20% is excreted in the feces. Less than 0.1% of the dose administered is excreted in urine as unchanged drug.
Six urinary metabolites have been detected. The two main metabolites have been identified as hydroxyomeprazole and the corresponding carboxylic acid. Three metabolites have been identified in plasma: the sulphide and sulphone derivatives and hydroxyomeprazole. It is unlikely that these metabolites contribute to inhibition of acid secretion.
Elderly subjects showed increased bioavailability (36%), reduced total plasma clearance (to 250 mL/min) and prolonged (50%) elimination half-life (to 1.0 hour) (data obtained from studies with i.v. administration of omeprazole and oral administration of omeprazole capsules). The mean urinary excretion of metabolites was 68% of the dose. These changes are consistent with reduction in pre-systemic and systemic elimination, typical in the elderly. The daily dose should, as a rule, not exceed 20 mg in this patient group (see WARNINGS AND PRECAUTIONS and DOSAGE AND ADMINISTRATION).
The pharmacokinetics of omeprazole in patients with impaired renal function was virtually the same as in healthy subjects (data obtained from studies with i.v. administration of omeprazole and oral administration of omeprazole capsules). However, patients with impaired liver function showed a 75% increase in bioavailability, reduced total plasma clearance (to 67 mL/min), and a four-fold prolongation of the elimination half-life (to 2.8 hours) (data obtained from studies with i.v. administration of omeprazole and oral administration of omeprazole capsules). A dose of 20 mg given once daily to these patients for 4 weeks was well tolerated. Dosage for patients with liver cirrhosis and other liver dysfunction should, as a rule, not exceed 20 mg daily (see
WARNINGS AND PRECAUTIONS and DOSAGE AND ADMINISTRATION).
Information on the bioavailability of omeprazole 20 mg tablet in elderly patients, in patients with hepatic insufficiency, and in patients with renal insufficiency is not currently available.
TOXICOLOGY
Acute Toxicity
| SPECIES | SEX | ROUTE | LD50 (mg/kg) | |||||||
| Mouse | M | p.o.1* | >4,000 | |||||||
| F | p.o.1* | >4,000 | ||||||||
| Mouse | M | p.o.1 | 1,520 | |||||||
| F | p.o.1 | 1,380 | ||||||||
| Mouse | M | i.v. | 83 | |||||||
| F | i.v. | >100 | ||||||||
| Rat | M | p.o.1* | >4,000 | |||||||
| F | p.o.1* | >4,000 | ||||||||
| Rat | M | p.o.1 | >5,010 | |||||||
| F | p.o.1 | 3,320 | ||||||||
| Rat | M | i.v. | >40 | |||||||
| F | i.v. | >40 | ||||||||
1 Suspension in Methocel®, not buffered
* Non-micronized test compound
The highest oral dose (4,000 mg/kg) of non-micronized omeprazole did not cause death in any of the species tested. With micronized omeprazole, suspended in Methocel®, the acute oral LD50 was approximately 1,500 mg/kg in mice; in male rats, higher than the maximum dose (5,000 mg/kg); and in female rats, approximately 3000 mg/kg. As much as 80% of the compound may not have been absorbed due to acid degradation of these single doses in the stomach. Death occurred within 2 days of ingestion and was preceded by reduced motor activity, reduced respiration frequency but increased respiration depth, reduced body temperature, and twitching, tremor or convulsions. The highest oral dose given to dogs (660 mg/kg) caused vomiting within 40-100 minutes of ingestion. The acute i.v. LD50 was 83 mg/kg in male mice, and in female mice >100 mg/kg. The corresponding figure in rats was >40 mg/kg. Death occurred within a few minutes of injection, preceded by cyanosis and convulsions.
Chronic Toxicity
The chronic toxicity of omeprazole was studied in mice, rats and dogs after oral and i.v. administration. Mice received oral doses of 14-140 mg/kg for up to 18 months, rats 14400 mg/kg for up to 24 months, and dogs 1-140 mg/kg for up to 12 months. Intravenous omeprazole was given to rats in doses of 2-16 mg/kg for up to one month and to 10 dogs in doses of 1-9 mg/kg for up to one month.
In the dog, a slight to moderate atrophy of the chief cells and rugal hypertrophy were observed. These changes were reversible after treatment cessation.
Following chronic i.v. administration of omeprazole to rats (~1.7-15.5 mg/kg/day) for one month and to dogs (~0.7-8.6 mg/kg/day) for one month, no treatment-related changes were observed.
In the rat, decreased plasma concentrations of triiodothyronine were observed in the two highest groups; TSH increased in the high-dose males. Lower doses had no significant effect. General hypertrophy of the oxyntic mucosa was found; the size of some chief cells was decreased and some granularity was observed. Both the hypertrophy and chief cell changes were reversible.
Mutagenicity
Omeprazole was tested in vivo (mouse micronucleus test, chromosome aberration in mice) and in vitro (Ames test, mouse lymphoma forward mutation assay), and showed no evidence of a mutagenic effect.
Carcinogenicity
An 18-month oral study was conducted in mice at doses of 14, 44 and 140 mg/kg/day. No evidence of carcinogenic potential was seen. A 24-month oral study was conducted in rats at doses of 14, 44 and 140 mg/kg/day. No increase in carcinomas was observed in any organ. However, there were dose- and time-dependent increases of tumour-like proliferations in the stomach. Histology showed a continuum from diffuse ECL-cell hyperplasia in the basal region of the gastric glands to less frequent micronoduli and occasional tumour-like proliferations, some extending into the sub-mucosa. The proliferations were classified as gastric carcinoids. The proliferation of ECL-cells and development of carcinoids were more frequent in female rats.
No metastases were identified in any of the animals. Carcinoids have not been observed after long-term administration of omeprazole to mice and dogs.
Gastric ECL-Cell Carcinoids
Extensive investigations have been carried out to explain the ECL-cell hyperplasia and the gastric carcinoid findings in rats. Gastrin produced by the G-cells in the antrum plays an important role in the feedback control of gastric acid secretion.
In one series of experiments, the antrum of rats was surgically excluded from the rest of the stomach. The removal of acid from the antrum in this way led to pronounced hypergastrinemia and, secondary to this, gastric ECL-cell proliferation. Antrectomy, which removes the source of gastrin, led to a decrease in gastric ECL-cell density. These experiments indicated that gastrin has a direct trophic effect on gastric ECL-cells. In another series of experiments, high doses of omeprazole and a histamine H2-receptor blocker caused hypergastrinemia and increased ECLcell density. In antrectomized rats given a high dose of omeprazole, plasma gastrin levels remained normal, and consequently there was no increase in ECL-cell density. It has therefore been concluded that (i) inhibition of gastric acid secretion by large doses of omeprazole or a histamine H2-receptor blocker evokes a natural feedback response leading to hypergastrinemia, (ii) long-standing hypergastrinemia leads to gastric ECL-cell proliferation, and (iii) there is no direct trophic effect of omeprazole on gastric ECL-cells.
An additional long-term (24 months) toxicity study in female rats (1.8-14 mg/kg/day) confirmed that the ECL-cell carcinoids were extreme end-life tumours and that there was a linear correlation between carcinoid incidence and dose of omeprazole (1.8-140 mg/kg/day). In rats given omeprazole 14 mg/kg/day for 12 months, no carcinoids were found, and the ECL-cell hyperplasia recovered to normal during the next 12 months of no treatment.
No carcinoids have been found in mice and in dogs following administration of 28 mg/kg/day for 7 years.
Investigation in man has demonstrated an initial moderate increase in gastrin levels during treatment with omeprazole, but no further increase occurred during long-term (up to 3 years) treatment. No significant changes have been found in the endocrine cells of the oxyntic gastric mucosa during short- or long-term treatment with omeprazole in man, to date. Chronic treatment of patients with Zollinger-Ellison syndrome with mean daily doses of omeprazole of 60 mg/day for up to 5 years has not influenced the pre-treatment hypergastrinemia, and no changes in the endocrine cells of the gastric mucosa have been found on repeat biopsies.
Reproductive and Developmental Toxicity
In studies with male and female rats given oral doses of up to 138 mg/kg/day (approximately 500 times the recommended human dose), fertility and reproductive performance were not affected.
In rabbits, increased embryo-lethality and fetal resorption were observed at maternotoxic doses of 69 and 138 mg/kg/day (250 and 500 times the human dose). No maternal or fetal toxicity was observed in pregnant rats treated at doses ranging from 13.8 to 138 mg/kg/day (50 to 500 times the human dose). In rats, a slight decrease in litter size at birth and slightly impaired postnatal viability and growth were observed in offspring resulting from parents treated with high doses of 138 mg/kg/day (500 times the human dose) of omeprazole. Similar effects were not seen at lower doses.
REFERENCES
- 1. Allgood LD, Grender JM, Shaw MJ, et al. Comparison of Prilosec OTC (omeprazole magnesium 20.6 mg) to placebo for 14 days in the treatment of frequent heartburn. J Clin Pharm Ther 2005; 30:105-12.
- 2. Andersson T. Pharmacokinetics, metabolism and interactions of acid pump inhibitors. Clin Pharmacokinet 1996; 31:9-28.
- 3. Armstrong D, Talley NJ, Lauritsen K, et al. The role of acid suppression in patients with endoscopy-negative reflux disease: The effect of treatment with esomeprazole or omeprazole. Ailment Pharmacol Ther 2004; 20:413-21.
- 4. Bardhan KD, Muller-Lissner S, Bigard MA, et al. Symptomatic gastro-oesophageal reflux disease: double-blind controlled study of intermittent treatment with omeprazole or ranitidine. Br Med J 1999; 18:502-7.
- 5. Bate CM, Griffin SM, Keeling PWN, et al. Reflux symptom relief with omeprazole in patients without unequivocal oesophagitis. Ailment Pharmacol Ther 1996; 10:547-55.
- 6. Brunner G, Creutzfeldt W. Omeprazole in the long-term management of patients with acidrelated diseases resistant to ranitidine. And J Gastroenterol 1989;24:101-5.
- 7. Cederberg C, Ekenved G, et al. Acid inhibitory characteristics of omeprazole in man. Scand J Gastroenterol 1985; 20 (108):105-12.
- 8. Chiba N, DeGara CJ, Wilkinson JM, Hunt RH. Speed of healing and symptom relief in grade II-IV gastroesophageal reflux disease: a meta-analysis. Gastroenterol 1997; 112:1789-1810.
- 9. Diav-Citrin O, Arnon J, Shechtman S, et al. The safety of proton pump inhibitors in pregnancy: a multicentre prospective controlled study. Aliment Pharmacol Ther 2005; 21:269-75.
- 10. Ekman L, Hansson E, et al. Toxicological studies on omeprazole. Scand J Gastroenterol 1985; 20 (108):53-69.
- 11. EMEA Public Statement EMEA/328956/2009, 29 May 2009.
- 12. Fendrick AM, Shaw M, Schachtel B, et al. Self-selection and use patterns of over-thecounter omeprazole for frequent heartburn. Clin Gastroenterol Hepatol 2004; 2:17-21.
- 13. Hameeteman W, Tytgat GN. Healing of chronic Barrett ulcers with omeprazole. Am J Gastroenterol 1986; 81:764-6.
- 14.
Hatlebakk JG, Hyggen A, Madsen PH, et al. Heartburn treatment in primary care:
randomized, double-blind study for 8 weeks. Br Med J 1999;319 :550-3.
- 15. Howden CW, Payton CD, et al. Antisecretory effect and oral pharmacokinetics of omeprazole in patients with chronic renal failure. Eur J Clin Pharmacol 1985; 28:637-40.
- 16. Hungin APS, Gunn SD, Bate CM, et al. A comparison of the efficacy of omeprazole 20 mg once daily with ranitidine 150 mg bd in the relief of gastro-oesophageal reflux disease in general practice. Br J Clin Res 1993; 4:73-88.
- 17. Kallen BA. Use of omeprazole during pregnancy – no hazard demonstrated in 955 infants exposed during pregnancy. Eur J Obstet Gynecol Reprod Biol 2001; 96:63-8.
- 18. Lalkin A, Loebstein R, Addis A, et al. The safety of omeprazole during pregnancy: a multicentre prospective controlled study. Am J Obstet Gynecol 1998;179:727-30.
- 19. Lamberts R, et al. Long-term omeprazole treatment in man. Effects on gastric endocrine cell population. Digestion 1988; 39:126-35.
- 20. Lind T, Havelund T, Carlsson R, et al. Heartburn without oesophagitis: efficacy of omeprazole therapy and features determining therapeutic response. Scand J Gastroenterol 1997; 32:974-9.
- 21. Marshall JK, Thompson AB, Armstrong D. Omeprazole for refractory gastroesophageal reflux disease during pregnancy and lactation. Can J Gastroenterol. 1998 Apr;12(3):225-7.
- 22. Regardh CG, Gabrielsson M, et al. Pharmacokinetics and metabolism of omeprazole in animals and man - an overview. Scand J Gastroenterol 1985; 20(108):79-94.
- 23. Richter JE, Peura D, Benjamin SB, et al. Efficacy of omeprazole for the treatment of symptomatic acid reflux disease without esophagitis. Arch Intern Med 2000; 160:1810-6.
- 24. Richter JE, Kahrilas PJ, Johanson J, et al. Efficacy and safety of esomeprazole compared with omeprazole in GERD patients with erosive esophagitis: a randomized controlled trial. Am J Gastroenterol 2001; 96:656-65.
- 25. Ruigomez A, Garcia Rodriguez LA, Cattaruzzi C, et al. Use of cimetidine, omeprazole and ranitidine in pregnant women and pregnancy outcomes. Am J Epidemiol 1999; 150:476-81.
- 26. Wallmark B, Lindberg P. Mechanism of action of omeprazole. ISI Atlas of Science: Pharmacology 1987; 1:158-60.
- 27. Venables TL, Newland RD, Patel AC, et al. Omeprazole 10 milligrams once daily, omeprazole 20 milligrams once daily or ranitidine 150 mg twice a day, evaluated as initial therapy for the relief of symptoms of GERD in General Practice. Scandinavian J Gastroenterol 1997; 32:965-73.