


Product Monograph - Tecta
RECENT MAJOR LABEL CHANGES
| 7.0 Warnings and Precautions, Immune | 03/2023 |
|---|
TABLE OF CONTENTS
Sections or subsections that are not applicable at the time of authorization are not listed.
RECENT MAJOR LABEL CHANGES ............................................................................................ 2
TABLE OF CONTENTS .............................................................................................................. 2
PART I: HEALTH PROFESSIONAL INFORMATION ...................................................................... 4
INDICATIONS ............................................................................................................... 4
Pediatrics ................................................................................................................ 4
Geriatrics ................................................................................................................ 4
CONTRAINDICATIONS ................................................................................................. 4
DOSAGE AND ADMINISTRATION ................................................................................. 4
Dosing Considerations ............................................................................................ 4
Recommended Dose and Dosage Adjustment ....................................................... 5
Administration ........................................................................................................ 6
Missed Dose ........................................................................................................... 6
OVERDOSAGE .............................................................................................................. 6
DOSAGE FORMS, STRENGTHS, COMPOSITION AND PACKAGING ................................. 6
WARNINGS AND PRECAUTIONS .................................................................................. 7
Special Populations............................................................................................... 10
7.1.1 Pregnant Women ........................................................................................... 10
7.1.2 Breast-feeding ................................................................................................ 11
7.1.3 Pediatrics ........................................................................................................ 11
7.1.4 Geriatrics ........................................................................................................ 11
ADVERSE REACTIONS ................................................................................................ 11
Adverse Reaction Overview .................................................................................. 11
Clinical Trial Adverse Reactions ............................................................................ 11
Less Common Clinical Trial Adverse Reactions ..................................................... 13
Abnormal Laboratory Findings: Hematologic, Clinical Chemistry and Other Quantitative Data ........................................................................................................... 16
Post-Market Adverse Reactions ........................................................................... 16
DRUG INTERACTIONS ................................................................................................ 17
Drug Interactions Overview .................................................................................. 17
Drug-Drug Interactions ......................................................................................... 17
Drug-Food Interactions ......................................................................................... 21
Drug-Herb Interactions ......................................................................................... 21
Drug-Laboratory Test Interactions ........................................................................ 21
CLINICAL PHARMACOLOGY ....................................................................................... 21

Mechanism of Action ...................................................................................... 21

Pharmacodynamics ........................................................................................ 22

Pharmacokinetics ........................................................................................... 24
STORAGE, STABILITY AND DISPOSAL ......................................................................... 26
SPECIAL HANDLING INSTRUCTIONS ........................................................................... 27
PART II: SCIENTIFIC INFORMATION ....................................................................................... 28
PHARMACEUTICAL INFORMATION ............................................................................ 28
CLINICAL TRIALS ........................................................................................................ 29

Clinical Trials by Indication ............................................................................. 29
Reduction of Gastric Acid Secretion ............................................................................... 29
Healing of Gastro-Esophageal Reflux Disease ................................................................ 29
Symptomatic Gastro-Esophageal Reflux Disease ........................................................... 31
Helicobacter pylori (H. pylori) Associated Duodenal Ulcer .............................................. 32
Relapse of Reflux Esophagitis ......................................................................................... 34
MICROBIOLOGY ........................................................................................................ 36
NON-CLINICAL TOXICOLOGY ..................................................................................... 37
PATIENT MEDICATION INFORMATION .................................................................................. 45
PART I: HEALTH PROFESSIONAL INFORMATION
INDICATIONS
TECTA® (pantoprazole magnesium) is indicated for the treatment of conditions where a reduction of gastric acid secretion is required, such as the following:
- Duodenal ulcer
- Gastric ulcer
- Reflux esophagitis
- Symptomatic gastro-esophageal reflux disease (such as, acid regurgitation and heartburn)
- Helicobacter pylori (H. pylori) associated duodenal ulcer
Pantoprazole, in combination with clarithromycin and either amoxicillin or metronidazole, is indicated for the treatment of patients with an active duodenal ulcer who are H. pylori positive (see 4 DOSAGE AND ADMINISTRATION and 14 CLINICAL TRIALS).
Pediatrics
Pediatrics (< 18 years of age): No data are available to Health Canada; therefore, Health Canada has not authorized an indication for pediatric use.
Geriatrics
Geriatrics (> 65 years of age): Based on the data submitted and reviewed by Health Canada, the safety and efficacy of TECTA® in geriatric patients has been established; therefore, Health Canada has authorized all indications for geriatric use (see 4 DOSAGE AND ADMINISTRATION; 7.1.4 Geriatrics).
CONTRAINDICATIONS
- Pantoprazole magnesium is contraindicated in patients who are hypersensitive to pantoprazole, substituted benzimidazoles, or to any ingredient in the formulation, including any non-medicinal ingredient, or component of the container. For a complete listing, see 6 DOSAGE FORMS, STRENGTHS, COMPOSITION AND PACKAGING.
- Pantoprazole magnesium is contraindicated with co-administration of rilpivirine. See 7 WARNINGS AND PRECAUTIONS, Drug Interactions with Antiretroviral Drugs and 9.4 Drug-Drug Interactions.
DOSAGE AND ADMINISTRATION
Dosing Considerations
- Patients should use the lowest dose and shortest duration of proton pump inhibitor (PPI) therapy appropriate to the condition being treated.
- Withdrawal of long-term PPI therapy can lead to aggravation of acid related symptoms and may result in rebound acid hypersecretion.
Recommended Dose and Dosage Adjustment
Duodenal Ulcer
- The recommended adult dose of TECTA® for the oral treatment of duodenal ulcer is 40 mg given once daily in the morning. Healing usually occurs within 2 weeks. For patients not healed after this initial course of therapy, an additional course of 2 weeks is recommended.
Gastric Ulcer
- The recommended adult oral dose of TECTA® for the oral treatment of gastric ulcer is 40 mg given once daily in the morning. Healing usually occurs within 4 weeks. For patients not healed after this initial course of therapy, an additional course of 4 weeks is recommended.
Helicobacter pylori Associated Duodenal Ulcer
- Pantoprazole/Clarithromycin/Metronidazole Triple Combination Therapy: The recommended dose for H. pylori eradication is treatment for seven days with TECTA® 40 mg together with clarithromycin 500 mg and metronidazole 500 mg, all twice daily.
- Pantoprazole/Clarithromycin/Amoxicillin Triple Combination Therapy: The recommended dose for H. pylori eradication is treatment for seven days with TECTA® 40 mg together with clarithromycin 500 mg and amoxicillin 1000 mg, all twice daily.
- When TECTA® is prescribed in combination with clarithromycin, amoxicillin or metronidazole for the eradication of an H. pylori infection, the Product Monograph for the antibiotics used should be consulted and followed.
Symptomatic Gastro-Esophageal Reflux Disease (GERD)
- The recommended adult oral dose for the treatment of symptoms of GERD, including heartburn and regurgitation, is TECTA® 40 mg once daily for up to 4 weeks. If significant symptom relief is not obtained in 4 weeks, further investigation is required.
Reflux Esophagitis
- The recommended adult oral dose of TECTA® is 40 mg, given once daily in the morning. In most patients, healing usually occurs within 4 weeks. For patients not healed after this initial course of therapy, an additional 4 weeks of treatment is recommended.
- Patients with healed gastroesophageal reflux disease, who require greater than usual maintenance doses of PPIs to avoid recurrence of reflux esophagitis, may consider 40 mg TECTA® once daily in the morning.
Geriatrics
- No dosage adjustment is recommended for elderly patients. The daily dose used in elderly patients, as a rule, should not exceed the recommended dosage regimens. See 10.3 Pharmacokinetics, Special Populations and Conditions.
Health Canada has not authorized an indication for pediatric use. See 1.1 Pediatrics.
Administration
TECTA® is formulated as an enteric-coated tablet. A whole tablet should not be chewed or crushed, and should be swallowed with fluid in the morning either before, during, or after breakfast.
Missed Dose
If a dose is forgotten, the missed dose should be taken as soon as possible unless it is close to the next scheduled dose. Two doses should never be taken at one time to make up for a missed dose; patients should just return to the regular schedule.
OVERDOSAGE
Some reports of overdosage with pantoprazole have been received. No consistent symptom profile was observed after ingestion of high doses of pantoprazole. Daily doses of up to 272 mg pantoprazole sodium intravenous (i.v.) and single doses of up to 240 mg i.v. administered over 2 minutes, have been administered and were well tolerated.
As pantoprazole is extensively protein bound, it is not readily dialyzable. In the case of overdosage with clinical signs of intoxication, apart from symptomatic and supportive treatment, no specific therapeutic recommendations can be made.
| For management of a suspected drug overdose, contact your regional poison control centre. |
|---|
DOSAGE FORMS, STRENGTHS, COMPOSITION AND PACKAGING
Table 1. Dosage Forms, Strengths, Composition and Packaging
TECTA® is available as enteric-coated tablets for oral administration. The tablets are yellow,
| Route of Administration | Dosage Form / Strength / Composition | Non-medicinal Ingredients |
| Oral | Tablet (Enteric-Coated), 40 mg pantoprazole (as pantoprazole magnesium) | Calcium Stearate, Crospovidone, Ferric Oxide, Hypromellose, Mannitol, Poly (ethylacrylate, methacrylic acid), Povidone, Propylene Glycol, Sodium Carbonate (Anhydrous), Titanium Dioxide, Triethyl Citrate. |
round, biconvex tablets marked 40 on one side, as they contain 40 mg pantoprazole. Tablets are available in bottles of 7 or 100 tablets, and in blisters of 7 and 30 tablets.
Not all pack sizes may be marketed.
WARNINGS AND PRECAUTIONS
General
In the presence of any alarm symptom (e.g. significant unintentional weight loss, recurrent vomiting, dysphagia, hematemesis, anemia, or melena) and when gastric ulcer is suspected, the possibility of malignancy should be excluded before therapy with TECTA® is instituted since treatment with pantoprazole magnesium may alleviate symptoms and delay diagnosis. Further investigation should be considered if symptoms persist despite adequate treatment. In long-term treatment, patients should be kept under regular surveillance.
Antibiotic Combination Therapy
Pseudomembranous colitis has been reported with nearly all antibacterial agents, including clarithromycin and amoxicillin, and may range in severity from mild to life threatening. Therefore, it is important to consider this diagnosis in patients who present with diarrhea subsequent to the administration of antibacterial agents.
Treatment with antibacterial agents alters the normal flora of the colon and may permit overgrowth of Clostridia. Studies indicate that a toxin produced by Clostridium difficile is a primary cause of “antibiotic-associated colitis”.
After the diagnosis of pseudomembranous colitis has been established, therapeutic measures should be initiated. Mild cases of pseudomembranous colitis usually respond to discontinuation of the drug alone. In moderate to severe cases, consideration should be given to management with fluids and electrolytes, protein supplementation, and treatment with an antibacterial drug clinically effective against Clostridium difficile colitis.
Clostridium Difficile-Associated Diarrhea
Decreased gastric acidity due to any means, including proton pump inhibitors (PPIs), increases gastric counts of bacteria normally present in the gastrointestinal tract. Treatment with PPIs can lead to an increased risk of gastrointestinal infections such as Salmonella, Campylobacter and Clostridium difficile.
An increased risk for Clostridium difficile infection (CDI) and Clostridium difficile-associated diarrhea (CDAD) has been observed in association with PPI use in several observational studies. CDI/CDAD should be considered in the differential diagnosis for diarrhea that does not improve. Additional risk factors for CDI and CDAD include recent hospitalization, the use of antibiotics, old age and the presence of co-morbidities.
Patients should be prescribed PPIs at the lowest dose and for the shortest duration required for the condition being treated and be reassessed to ascertain whether continued PPI therapy remains beneficial.
Concomitant Use with Methotrexate
Literature suggests that concomitant use of PPIs with methotrexate (primarily at high dose) may elevate and prolong serum levels of methotrexate and/or its metabolite, possibly leading to methotrexate toxicities. A temporary withdrawal of the PPI may be considered in some patients receiving treatments with high dose methotrexate. See 9.4 Drug-Drug Interactions, methotrexate.
Carcinogenesis and Mutagenesis
Effects of long-term treatment include hypergastrinemia, possible enterochromaffin-like (ECL) cell hyperplasia and carcinoid formation in the stomach, adenomas and carcinomas in the liver and neoplastic changes in the thyroid.
In the rat, the mechanism leading to the formation of gastric carcinoids is considered to be due to the elevated gastrin level occurring during chronic treatment. Similar observations have also been made after administration of other acid secretion inhibitors. For further details, see 16 NON-CLINICAL TOXICOLOGY.
Short-term and long-term treatment with pantoprazole sodium in a limited number of patients up to 6 years have not resulted in any significant pathological changes in gastric oxyntic exocrine cells.
Drug Interactions with Antiretroviral Drugs
PPIs have been reported to interact with some antiretroviral drugs. The clinical importance and the mechanisms behind these interactions are not always known. A change in gastric pH may change the absorption of the antiretroviral drug. Other possible mechanisms are via CYP2C19. See 9.4 Drug-Drug Interactions.
Rilpivirine
Co-administration is contraindicated due to significant decrease in rilpivirine exposure and loss of therapeutic effect. See 2 CONTRAINDICATIONS.
Atazanavir and Nelfinavir
Co-administration with atazanavir or nelfinavir is not recommended due to decreased atazanavir and nelfinavir exposure (see the REYATAZ® and VIRACEPT® Product Monographs).
If the combination of TECTA® with atazanavir is judged unavoidable, close clinical monitoring is recommended in combination with the use of 400 mg atazanavir/100 mg ritonavir dose; the dose of TECTA® should not exceed an equivalent dose of omeprazole of 20 mg daily (see REYATAZ® Product Monograph).
Saquinavir
If TECTA® is co-administered with saquinavir/ritonavir, caution and monitoring for potential saquinavir toxicities, including gastrointestinal symptoms, increased triglycerides, deep vein thrombosis and QT prolongation, are recommended. Dose reduction of saquinavir should be considered from the safety perspective for individual patients (see INVIRASE® Product Monograph).
Endocrine and Metabolism
Hypomagnesemia
Hypomagnesemia, symptomatic and asymptomatic, has been reported in patients treated with PPIs for at least three months, in most cases after a year of therapy. Serious adverse events include tetany, arrhythmias, and seizures. Hypomagnesemia may lead to hypocalcemia and/or hypokalemia. See 8.5 Post-Market Adverse Reactions. In most patients, treatment of hypomagnesemia required magnesium replacement and discontinuation of the PPI.
For patients expected to be on prolonged treatment or who take PPIs with medications such as digoxin or drugs that may cause hypomagnesemia (e.g., diuretics), healthcare professionals may consider monitoring magnesium levels prior to initiation of PPI treatment and periodically.
The chronic use of PPIs may lead to hypomagnesemia.
Cyanocobalamin (Vitamin B12) Deficiency
The prolonged use of PPIs may impair the absorption of protein-bound Vitamin B12 and may contribute to the development of cyanocobalamin (Vitamin B12) deficiency (see 9.2 Drug Interactions Overview, Other).
Gastrointestinal
Long-term use of TECTA® is associated with an increased risk of fundic gland polyps, especially beyond one year. See 8.5 Post-Market Adverse Reactions. Most fundic gland polyps are asymptomatic. Use the lowest dose and shortest duration of PPI therapy appropriate to the condition being treated.
Hepatic/Biliary/Pancreatic
Pantoprazole 40 mg daily is not recommended in patients with severe liver disease. For more details, please see, 10.3 Pharmacokinetics, Special Populations and Conditions.
Pantoprazole should not be used in combination treatment for the eradication of H. pylori in patients with severe hepatic dysfunction since currently no data are available on the efficacy and safety of pantoprazole in combination treatment of these patients.
Immune
Severe cutaneous adverse reactions
Severe cutaneous adverse reactions (SCARs), including erythema multiforme, Stevens-Johnson syndrome (SJS), toxic epidermal necrolysis (TEN), drug reaction with eosinophilia and systemic symptoms (DRESS), and acute generalized exanthematous pustulosis (AGEP) have been reported in association with the use of PPIs. Discontinue pantoprazole at the first signs or symptoms of SCARs or other signs of hypersensitivity and consider further evaluation. At the time of prescription, patients should be informed of the signs and symptoms, and advised to monitor closely for skin reactions. See 8.5 Post-Market Drug Reactions.
Subacute cutaneous lupus erythematosus
Subacute cutaneous lupus erythematosus (SCLE) has been reported with the use of PPIs. If lesions occur, especially in sun-exposed areas of the skin, and if accompanied by arthralgia, the patient should seek medical help promptly and the health care professional should consider stopping TECTA®. The occurrence of SCLE with previous PPI treatment may increase the risk of SCLE with other PPIs. See 8.5 Post-Market Drug Reactions.
Monitoring and Laboratory Tests
During treatment with antisecretory drugs, chromogranin A (CgA) increases due to decreased gastric acidity. Increased CgA levels may interfere with investigations for neuroendocrine tumours. To avoid this interference, TECTA® treatment should be stopped 14 days before CgA measurements. See 9 DRUG INTERACTIONS.
Musculoskeletal
Bone Fracture: Several published observational studies suggest that PPI therapy may be associated with an increased risk for osteoporosis-related fractures of the hip, wrist, or spine. The risk of fracture was increased in patients who received high-dose, defined as multiple daily doses, and long-term PPI therapy (a year or longer). Patients should use the lowest dose and shortest duration of PPI therapy appropriate to the condition being treated. Patients at risk for osteoporosis-related fractures should be managed according to established treatment guidelines. See 4 DOSAGE AND ADMINISTRATION and 8 ADVERSE REACTIONS.
Renal
The daily dose used in renal insufficient patients, as a rule, should not exceed the recommended dosage regimens. See 10.3 Pharmacokinetics, Special Populations and Conditions.
Pantoprazole should not be used in combination treatment for the eradication of H. pylori in patients with renal dysfunction since currently no data are available on the efficacy and safety of pantoprazole in combination treatment of these patients.
Skin
See 7 WARNINGS AND PRECAUTIONS, Immune.
Special Populations
7.1.1 Pregnant Women
There are no adequate or well-controlled studies in pregnant women. Studies in animals have shown reproductive toxicity, the potential risk for humans is unknown. TECTA® should not be administered to pregnant women unless the expected benefits outweigh the potential risks to the fetus. See also 16 NON-CLINICAL TOXICOLOGY, Reproductive and Developmental Toxicology.
7.1.2 Breast-feeding
Animal studies have shown excretion of pantoprazole in breast milk. Excretion into human milk has been reported. Pantoprazole should not be given to nursing mothers unless its use is believed to outweigh the potential risks to the infant. See also 16 NON-CLINICAL TOXICOLOGY, Reproductive and Developmental Toxicology.
7.1.3 Pediatrics
Pediatrics (< 18 years of age): No data are available to Health Canada; therefore, Health Canada has not authorized an indication for pediatric use.
7.1.4 Geriatrics
Geriatrics (> 65 years of age): No dose adjustment is recommended based on age. The daily dose used in elderly patients, as a rule, should not exceed the recommended dosage regimens. See 10.3 Pharmacokinetics, Special Populations and Conditions.
Benefits of use of PPIs should be weighed against the increased risk of fractures as patients in this category (> 71 years of age) may already be at high risk for osteoporosis-related fractures. If the use of PPIs is required, they should be managed carefully according to established treatment guidelines. See 4 DOSAGE AND ADMINISTRATION and 8 ADVERSE REACTIONS.
ADVERSE REACTIONS
Adverse Reaction Overview
TECTA® (pantoprazole magnesium) is well tolerated. Most adverse events have been mild and transient showing no consistent relationship with treatment.
The following adverse events (the most frequently reported) have been reported in individuals receiving pantoprazole sodium therapy (40 mg once daily) in controlled clinical trials of at least 6 months duration: Headache (2.1%), Diarrhea (1.6%), Nausea (1.2%).
No differences in adverse reactions are expected between pantoprazole magnesium and pantoprazole sodium.
Clinical Trial Adverse Reactions
Clinical trials are conducted under very specific conditions. Therefore, the adverse reaction rates observed in the clinical trials may not reflect the rates observed in practice and should not be compared to the rates in the clinical trials of another drug. Adverse reaction information from clinical trials may be useful in identifying and approximating rates of adverse drug reactions in real-world use.
In a short term study (40 mg pantoprazole magnesium tablet, once daily for 7 days) in patients with GERD, and in a 4 to 8-week clinical trial in 636 GERD patients, the adverse event profile seen with TECTA® (pantoprazole magnesium) 40 mg tablet was similar to that seen with the pantoprazole sodium 40 mg tablet.
No differences in adverse reactions are expected between pantoprazole magnesium and pantoprazole sodium.
Adverse events have been recorded during controlled clinical investigations in 13000 patients exposed to pantoprazole sodium as the single therapeutic agent for treatment of conditions requiring acid suppression.
The following adverse reactions considered possibly, probably, or definitely related by the investigator have been reported in individuals receiving pantoprazole sodium therapy (20 mg or 40 mg once daily) in long-term clinical trials (duration of at least 6 months).
There were a limited number of H. pylori positive patients in these studies and therefore, definitive conclusions with regard to long-term consequences of H. pylori infection and acid suppressive treatment on gastric inflammation in this sub-group cannot be made.
Table 2. Adverse drug reactions with a frequency of ≥ 1% related to 40 mg pantoprazole sodium, assessed as possibly, probably or definitely related by the investigator
| Preferred term | Number of patients | Percentage of patients |
|---|---|---|
| Headache | 24 | 2.1 |
| Diarrhea | 18 | 1.6 |
| Nausea | 13 | 1.2 |
In addition, the following adverse events with a frequency of ≥ 1% considered unrelated, or unlikely related by the investigator have been reported in individuals receiving pantoprazole sodium therapy (20 mg or 40 mg once daily) in short-term and long-term clinical trials.
Table 3. Adverse Events with a frequency of >1%, 20 or 40 mg pantoprazole sodium
| Gastrointestinal Disorders: | Diarrhea |
|---|---|
| General Disorders | Influenza Like Illness |
| Nervous System Disorders | Headache |
A total of 1217 patients were treated with triple combination therapy including pantoprazole sodium and two antibiotics. Adverse events noted at a frequency of greater than or equal to 1% when pantoprazole sodium was used in combination with antibiotics for the eradication of an H. pylori infection included the following:
Table 4. Adverse Events with a frequency ≥1% related to pantoprazole sodium in combination with antibiotics
| Body System | In combination with clarithromycin and metronidazole (n = 725) | In combination with amoxicillin and clarithromycin (n = 492) |
|---|---|---|
| Body as a Whole: | Headache (1.8%), Tiredness (1.1%) | Headache (1.8%), Pain (1.0%) |
| Central and Peripheral Nervous System: | Dizziness (1.4%) | |
| Skin and Appendages: | Exanthema (1.2%) | |
| Gastrointestinal Disorders: | Diarrhea (4.8%), Nausea (3.7%), Upper abdominal pain (1.9%), Tongue pain (1.2%), Loose stools (1.0%), Buccal inflammation (1.0%) | Diarrhea (10.0%), Bitter taste (3.0%), Upper abdominal pain (1.4%), Nausea (1.2%) |
| Hepatobiliary Disorders: | Hepatic enzymes increased (1.2%) | |
| Special Senses: | Bitter taste (4.0%), Metallic taste (2.1%) |
Regardless of the combination regimen, the most frequently reported events were gastrointestinal system disorders, followed by autonomic nervous system disorders and “body as a whole”, or generalized disorders.
Less Common Clinical Trial Adverse Reactions
Other adverse drug reactions that were reported for 40 mg pantoprazole sodium in controlled studies at an incidence of 0.1 to 1% are listed below by body system:
| Cardiovascular System: | Blood pressure increased, Hypertension, ECG abnormal |
|---|---|
| Gastrointestinal Disorders: | Flatulence, Abdominal distension, Abdominal pain, Abdominal pain upper, Loose stools, Esophageal reflux aggravated, Gastric polyps, Abdominal discomfort, Abdominal tenderness, Constipation, Eructation, Vomiting, Dyspepsia, Gastroesophageal reflux, Esophagitis |
| General Disorders: | Fatigue, Peripheral edema, Pyrexia |
| Hepatobiliary Disorders: | Alanine aminotransferase increased, Aspartate aminotransferase increased, Liver function tests abnormal, Transaminases increased |
| Laboratory Parameters: | Hypertriglyceridemia |
| Metabolism and Nutrition Disorders: | Appetite decreased, Weight increase |
| Nervous System Disorders: | Dysgeusia, Dizziness, Migraine, Vertigo |
| Respiratory System: | Cough |
| Skin and Subcutaneous Tissue Disorders: | Pruritus, Rash |
| Special Senses: | Mouth dry, Vision blurred |
| Other: | Neoplasm |
The following adverse reactions considered possibly, probably, or definitely related by the investigator reported in individuals receiving pantoprazole therapy (20 mg or 40mg pantoprazole sodium once daily), in short-term clinical trials (duration of up to 3 months), with a frequency of 0.1 to 1% are listed below by body system:
| Gastrointestinal Disorders: | Diarrhea, Flatulence, Nausea, Constipation, Abdominal pain |
|---|---|
| Nervous System Disorders: | Headache, Dizziness |
| Skin and Subcutaneous Tissue Disorders: | Pruritus |
The following serious adverse events regardless of causality in individuals receiving pantoprazole therapy (20 mg or 40 mg pantoprazole sodium once daily), reported with a frequency of <0.1% are listed below by body system:
| Infections and Infestations | Sepsis |
|---|
In addition the following identified adverse drug reactions have been reported in oral pantoprazole sodium clinical trials in any indication and in any dosage:
| SOC | Uncommon (infrequent): ≥ 1/1,000 to < 1/100 (≥0.1% and <1%); | Rare: ≥1/10,000 and <1/1,000 (≥0.01% and <0.1%) | Very rare: <1/10,000 (<0.01%), including isolated reports |
|---|---|---|---|
| Blood and Lymphatic system Disorders | Agranulocytosis | Thrombocytopenia; Leukopenia; Pancytopenia | |
| Eye Disorders | Disturbances in vision/blurred vision | ||
| Gastrointestinal Disorders: | Nausea/vomiting; Abdominal distension and bloating; Constipation; Dry mouth; Abdominal pain and discomfort | ||
| General Disorders and Administration Site Conditions | Asthenia, fatigue and malaise | Body temperature increased; Edema peripheral | |
| Hepatobiliary Disorders | Liver enzymes increased (transaminases, γ-GT) | Bilirubin increased | |
| Immune System Disorders | Hypersensitivity (including anaphylactic reactions and anaphylactic shock) | ||
| Metabolism and Nutrition Disorders | Hyperlipidemias and lipid increases (triglycerides, cholesterol); Weight changes | ||
| Musculoskeletal and Connective Tissue Disorders | Myalgia; Arthralgia | ||
| Nervous System Disorders: | Headache, Dizziness | Taste disorder | |
| Psychiatric Disorders | Sleep disorders | Depression (and all aggravations) | Disorientation (and all aggravations) |
| Reproductive System and Breast Disorders | Gynecomastia |
| SOC | Uncommon (infrequent): ≥ 1/1,000 to < 1/100 (≥0.1% and <1%); | Rare: ≥1/10,000 and <1/1,000 (≥0.01% and <0.1%) | Very rare: <1/10,000 (<0.01%), including isolated reports |
|---|---|---|---|
| Skin and Subcutaneous Tissue Disorders | Rash/exanthema/eruption; Pruritus | Urticaria; Angioedema |
Abnormal Laboratory Findings: Hematologic, Clinical Chemistry and Other Quantitative Data
Please refer to the Hepatobiliary Disorders and Laboratory Parameters subsection in
8 ADVERSE REACTIONS. See also 7 WARNINGS AND PRECAUTIONS, Hepatic/Biliary/Pancreatic and 10.3 Pharmacokinetics, Special Populations and Conditions.
Post-Market Adverse Reactions
The following adverse events were reported in post-marketing use and causal relation to pantoprazole sodium treatment could not be ruled out. As the events were reported spontaneously, no exact incidences can be provided:
| Blood and Lymphatic System Disorders | Eosinophilia |
|---|---|
| Ear and Labyrinth Disorders | Tinnitus |
| Eye Disorders | Photophobia |
| Gastrointestinal Disorders: | Pancreatitis; Increased salivation; Microscopic colitis |
| Hepatobiliary Disorders | Hepatocellular injury; Jaundice; Hepatocellular failure |
| Investigations | Elevated creatine phosphokinase |
| Metabolism and Nutrition Disorders | Hyponatremia; Hypomagnesemia; Hypocalcemia*; Hypokalemia*; Increased appetite |
| Musculoskeletal and Connective Tissue Disorders | Osteoporosis and osteoporosis-related fractures; Rhabdomyolysis |
| Nervous System Disorders: | Anterior ischemic optic neuropathy; Speech disorder; Tremor; Paresthesia |
| Psychiatric Disorders | Hallucination; Confusion (especially in pre-disposed patients, as well as the aggravation of these symptoms in the case of pre-existence); Nervousness |
| Renal and Urinary Disorders | Tubulointerstitial nephritis (TIN) (with possible progression to renal failure); Hematuria |
| Reproductive System and Breast Disorders | Impotence |
| Skin and Subcutaneous Tissue Disorders | Stevens-Johnson syndrome (SJS); Erythema multiforme; Toxic epidermal necrolysis (TEN; Lyell syndrome); Photosensitivity; DRESS syndrome (Drug Reaction with Eosinophilia and Systemic Symptoms) (some fatal); Acute generalized Exanthematous pustulosis (AGEP)**; Alopecia; Acne; Exfoliative dermatitis |
|---|
* May be related to the occurrence of Hypomagnesemia, **See 7 WARNINGS AND PRECAUTIONS, Immune.
There have been post-marketing reports of severe cutaneous adverse reactions (SCARs) and subacute cutaneous lupus erythematosus (SCLE). See 7 WARNINGS AND PRECAUTIONS, Immune.
There have been post-marketing reports of fundic gland polyps (FGPs). See 7 WARNINGS AND PRECAUTIONS, Gastrointestinal.
DRUG INTERACTIONS
Drug Interactions Overview
Pantoprazole undergoes extensive hepatic metabolism via cytochrome P450-mediated oxidation. The main metabolic pathway is demethylation by CYP2C19 and other metabolic pathways which include oxidation by CYP3A4. This is followed by sulphate conjugation via a Phase II reaction (non-saturable, non-cytochrome P450 dependent). Pharmacokinetic drug interaction studies in man did not demonstrate the inhibition of the oxidative metabolism of the drug. No induction of the CYP 450 system by pantoprazole was observed during chronic administration of pantoprazole sodium with antipyrine as a marker. Pantoprazole causes long lasting inhibition of gastric acid secretion. Therefore, pantoprazole may interfere with absorption of drugs where gastric pH is an important determinant of the bioavailability (e.g. ketoconazole, itraconazole, posaconazole, erlotinib).
Other: Generally, daily treatment with any acid-blocking medicines over a long time (e.g. longer than 3 years) may lead to malabsorption of cyanocobalamin caused by hypo- or achlorhydria. Rare cases of cyanocobalamin deficiency under acid-blocking therapy have been reported in the literature and should be considered if respective clinical symptoms are observed. See 7 Warnings and Precautions, Cyanocobalamin (Vitamin B12) Deficiency.
Drug-Drug Interactions
The drugs listed in this table are based on either drug interaction case reports or studies, or potential interactions due to the expected magnitude and seriousness of the interaction (i.e., those identified as contraindicated).
The magnesium content of a 40 mg tablet is negligibly low and thus far below the amount of magnesium taken with food or dietary supplements. No differences in drug-drug interactions are expected between pantoprazole magnesium and pantoprazole sodium.
Table 5. Established or potential drug-drug interactions
| Concomitant Drug Name | Source of Evidence | Effect | Clinical comment |
|---|---|---|---|
| Antibiotics (amoxicillin, clarithromycin and metronidazole) | CT | No clinical effect | See 7 WARNINGS AND PRECAUTIONS, General, Antibiotic Combination Therapy. No pharmacokinetic interaction was observed between pantoprazole sodium and the following antibiotic combinations: metronidazole plus clarithromycin, metronidazole plus amoxicillin, amoxicillin plus clarithromycin. In single dose pharmacology studies, concomitant administration of pantoprazole sodium with combinations of amoxicillin, clarithromycin, and/or metronidazole, in fasted healthy volunteers showed a lack of interaction. Antibiotic combination therapy was well tolerated, with no clinically relevant changes in vital signs, ECG, or clinical laboratory parameters. Equivalence between the test (i.e., in combination regimen) and the respective reference (i.e., subject medication) was concluded when the 90% CI was within the equivalence range of 0.67 to 1.50 for the AUC0-∞ and Cmax. The ratio of test/reference point estimates (90% CI), in concomitant administration of the following were:
|
| Concomitant Drug Name | Source of Evidence | Effect | Clinical comment | |
|---|---|---|---|---|
In a preclinical study, pantoprazole sodium in combination therapy with various antibiotics (including tetracycline, clarithromycin, and amoxicillin) was shown to have a potentiating effect on the elimination rate of H. pylori infection. See 15 MICROBIOLOGY. | ||||
| Antacids | CT | No clinical effect | Concomitant use of antacids does not affect the pharmacokinetics of pantoprazole sodium. | |
| Antiretroviral Drugs | T | ↓rilpivirine, atazanavir, nelfinavir ↑saquinavir | See 7 WARNINGS AND PRECAUTIONS, Drug Interactions with Antiretroviral Drugs. Rilpivirine: Co-administration is contraindicated due to significant decreases in rilpivirine exposure and loss of therapeutic effect. See 2 CONTRAINDICATIONS. Atazanavir: Co-administration of TECTA® with atazanavir is not recommended. Concomitant administration of omeprazole (20 or 40 mg once daily) substantially reduced plasma Cmax and AUC of atazanavir in healthy volunteers administered atazanavir or atazanavir/ritonavir. See REYATAZ® Product Monograph. Nelfinavir: Co-administration of TECTA® with nelfinavir is not recommended. Concomitant administration of omeprazole (40 mg daily) with nelfinavir (1250 mg twice daily) markedly reduced the AUC and Cmax for nelfinavir (by 36% and 37%, respectively) and | |
| Concomitant Drug Name | Source of Evidence | Effect | Clinical comment |
|---|---|---|---|
its active metabolite M8 (by 92% and 89%, respectively). See VIRACEPT® Product Monograph. Saquinavir: Co-administration of saquinavir requires caution and monitoring, along with potential dose reduction of saquinavir, due to increased saquinavir exposure and thus the risk of saquinavir-related toxicities (see the INVIRASE® Product Monograph). Concomitant administration of omeprazole (40 mg daily) with saquinavir/ritonavir (1000/100 mg twice daily) increased saquinavir AUC by 82% and Cmax by 75%. | |||
| Methotrexate | C | - | Case reports, published population pharmacokinetic studies, and retrospective analyses suggest that concomitant administration of PPIs and methotrexate (primarily at high dose) may elevate and prolong serum levels of methotrexate and/or its metabolite hydroxymethotrexate. However, no formal drug interaction studies of methotrexate with PPIs have been conducted. See 7 WARNINGS AND PRECAUTIONS, General, Concomitant Use with Methotrexate. |
| Warfarin | C, CT | ↑ INR and PT | No interaction during concomitant administration of warfarin has been observed in clinical pharmacokinetic studies. However, a few isolated cases of changes in INR have been reported in the post-marketing period. Therefore, in patients being treated with coumarin anticoagulants, monitoring of prothrombin time (PT)/INR is recommended after initiation, termination or during irregular use of pantoprazole. |
C = Case Study; CT = Clinical Trial; T = Theoretical; INR = International normalized ratio
Cytochrome P450 Interactions
Pantoprazole sodium does not interact with carbamazepine, caffeine, diclofenac, naproxen, piroxicam, ethanol, glibenclamide, metoprolol, antipyrine, diazepam, phenytoin, nifedipine, theophylline, digoxin, oral contraceptives (containing levonorgestrel and ethinyl oestradiol), or cyclosporine.
Drug-Food Interactions
Consumption of food does not affect the pharmacokinetics (AUC and Cmax) of pantoprazole sodium. See 10.3 Pharmacokinetics.
Drug-Herb Interactions
Interactions with herbal products have not been established.
Drug-Laboratory Test Interactions
There have been reports of false-positive results in urine screening tests for tetrahydrocannabinol (THC) in patients receiving most PPIs, including pantoprazole. To some extent, a cross-reactivity of PPIs to the THC assay in the OnTrak TesTcard™ 9 has been seen, though this may not be limited to this screening test. In order to verify positive urine screening results, a confirmatory method should be considered.
During treatment with antisecretory drugs, chromogranin A (CgA) increases due to decreased gastric acidity. Increased CgA level may interfere with investigations for neuroendocrine tumours. To avoid this interference, TECTA® treatment should be stopped 14 days before CgA measurements. See 7 WARNINGS AND PRECAUTIONS, Monitoring and Laboratory Tests and 10.2 Pharmacodynamics, Pharmacodynamic Properties.
CLINICAL PHARMACOLOGY
 Mechanism of Action
TECTA® (pantoprazole magnesium) is a specific inhibitor of the gastric H+, K+-ATPase enzyme (the proton pump) that is responsible for gastric acid secretion by the parietal cells of the stomach.
Pantoprazole is a substituted benzimidazole that accumulates in the acidic environment of the parietal cells after absorption. Pantoprazole is then converted into the active form, a cyclic sulphenamide, which binds selectively to the proton translocating region of the H+, K+-ATPase, thus inhibiting both the basal and stimulated gastric acid secretion. Pantoprazole exerts its effect in an acidic environment (pH < 3), and it is mostly inactive at higher pH. Its pharmacological and therapeutic effect is achieved in the acid-secretory parietal cells. As pantoprazole action is distal to the receptor levels, it can inhibit gastric acid secretion irrespective of the nature of the stimulus (e.g., acetylcholine, histamine, gastrin).
Fasting gastrin values increased during pantoprazole sodium treatment, but in most cases the increase was only moderate. An extensive evaluation of clinical laboratory results has not revealed any clinically important changes during pantoprazole sodium treatment (except for gastrin which increased to 1.5-fold after 4 to 8 weeks).
Treatment with pantoprazole sodium alone has a limited effect on infections of H. pylori, a bacterium implicated as a major pathogen in peptic ulcer disease. Approximately 90-100% of patients with duodenal ulcers, and 80% of patients with gastric ulcers, are H. pylori positive. Preclinical evidence suggests that there is a synergistic effect between pantoprazole sodium and selected antibiotics in eradicating H. pylori. In infected patients, eradication of the infection with pantoprazole sodium and appropriate antibiotic therapy leads to ulcer healing, accompanied by symptom relief and a decreased rate of ulcer recurrence.
In single dose clinical pharmacology studies, pantoprazole sodium was administered concomitantly with combinations of amoxicillin, clarithromycin, and/or metronidazole. When a single dose of pantoprazole sodium was administered to healthy volunteers in combination with metronidazole plus amoxicillin, with clarithromycin plus metronidazole, or with clarithromycin plus amoxicillin, lack of interaction between any of the medications was shown.
 Pharmacodynamics
Daily oral doses of pantoprazole magnesium 40 mg tablet showed a consistent and effective acid control. Information from a pharmacodynamic trial in patients with GERD indicates that TECTA® (pantoprazole magnesium) 40 mg tablets demonstrate similar 24-hour inhibition of acid secretion, and effect on intragastric pH, as pantoprazole sodium 40 mg tablets.
In clinical studies investigating i.v. and oral administration, pantoprazole sodium inhibited pentagastrin-stimulated gastric acid secretion. With a daily oral dose of 40 mg, inhibition was 51% on Day 1 and 85% on Day 7. Basal 24-hour acidity was reduced by 37% and 98% on Days 1 and 7, respectively.
Pharmacodynamic Properties:
During treatment with antisecretory medicinal products, serum gastrin increases in response to the decreased acid secretion. Also CgA increases due to decreased gastric acidity. The increased CgA level may interfere with investigations for neuroendocrine tumours.
Available published evidence suggests that PPIs should be discontinued 14 days prior to CgA measurements. This is to allow CgA levels that might be spuriously elevated following PPI treatment to return to reference range. See 7 WARNINGS AND PRECAUTIONS, Monitoring and Laboratory Tests.
A pharmacodynamic trial in patients with GERD (n = 79) was performed to study the effect of pantoprazole magnesium and pantoprazole sodium on 24-hour intragastric pH. The primary objective of this study was to compare the 24-hour intragastric pH profile under steady-state conditions following administration of pantoprazole magnesium versus pantoprazole sodium administered as a 1 x 40 mg enteric-coated tablet once daily for 7 consecutive days each in adult symptomatic GERD patients (Savary-Miller stage I-III). The primary criterion for efficacy was the percentage of time with intragastric pH>4.
Results from this trial indicate that TECTA® (pantoprazole magnesium) 40 mg tablets demonstrate similar inhibition of acid secretion (day and night), and effect on intragastric pH, as pantoprazole sodium 40 mg tablets.
Table 6. Equivalence Analysis Pantoprazole Magnesium vs. Pantoprazole Sodium
| Difference1 | 95% C.I.2 | Acceptance Region3 | Intra-Subject CV (%) | Inter- Subject CV (%) | |
| H. Pylori negative subjects | -2.40 | -4.99 to 0.18 | (-5.12, 5.12) | 18.15 % | 29.74 % |
| H. Pylori positive subjects | -0.60 | -7.20 to 6.01 | (-10.69, 10.69) | 12.29 % | 19.16 % |
CV – co-efficient of variation
1 Calculated using least-squares means (untransformed data)
2 95% Classic confidence interval for difference (untransformed data)
3 Acceptance region defined as +/- 15% of the Reference least-squares mean
Pantoprazole is a potent inhibitor of gastric acid secretion. This was demonstrated with pantoprazole sodium by use of a gastric acid aspiration technique as well as by continuous intragastric pH monitoring. Using the aspiration technique it was also shown that pantoprazole sodium caused a dose-dependent reduction of secreted gastric acid volume.
Table 7. Percent inhibition of pentagastrin-stimulated acid output (PSAO) in healthy volunteers following single oral doses of pantoprazole sodium vs. placebo during 4 to 7 hours post dosing.
| Dose | Mean % Inhibition of PSAO |
| 6 mg | 13% |
| 10 mg | 24% |
| 20 mg | 27% |
| 40 mg | 42% |
| 60 mg | 54% |
| 80 mg | 80% |
| 100 mg | 82% |
With 40 mg administered orally, effective inhibition of gastric acid secretion was achieved. Pantoprazole sodium 40 mg was significantly superior to standard H2-blocker therapy (300 mg ranitidine at night) with regard to median 24-hour and daytime pH; however, not for nighttime measurements.
Table 8. Effects of one week oral treatment in healthy volunteers with placebo, pantoprazole sodium 40 mg in the morning, and standard ranitidine therapy with 300 mg in the evening.
| Time of Day | Median pH | |||
| Placebo | Pantoprazole 40 mg | Ranitidine 300 mg | ||
| 08.00-08.00 (24h) | 1.6 | 4.2* | 2.7 | |
| 08.00-22.00 (Daytime) | 1.8 | 4.4* | 2.0 | |
| 22.00-08.00 (Nighttime) | 1.3 | 3.1 | 3.7 | |
* p<0.05 vs ranitidine
Increasing the once daily dose from 40 mg to 80 mg pantoprazole sodium did not result in a significantly higher median 24-hour pH.
Table 9. Effect of oral pantoprazole sodium in healthy volunteers on median 24 hour pH on Day 7 (40 vs 80 mg).
| 40 mg | 80 mg | |
| 3.8 | 3.85 | n.s. |
n.s. = not significant
Hence, once daily administration of 40 mg pantoprazole should be sufficient for the treatment of most patients with acid-related diseases.
 Pharmacokinetics
Table 10. Mean (SD, n=42) Pharmacokinetic Parameters for Healthy Adult Subjects After a Single Oral Administration of TECTA®
Dose (mg) | Cmax (µg/mL) | tmax (h) | t1/2 (h) | AUC (µg·h/mL) |
|---|---|---|---|---|
| 40 | 1.38 (0.68) | 6.29 (2.34) | 1.16 (0.83) | 3.90 (4.35) |
Pantoprazole magnesium and pantoprazole sodium are not bioequivalent in terms of plasma AUC and Cmax. In healthy, adult male volunteers, kinetic studies comparing the two salts show that the AUC of pantoprazole magnesium is almost 100% relative to that of pantoprazole sodium, under both fed and fasted conditions. Cmax is lower for pantoprazole magnesium (approximately 65 – 73% of pantoprazole sodium values).
Pantoprazole sodium shows linear pharmacokinetics, i.e., AUC and Cmax increase in proportion with the dose within the dose-range of 10 to 80 mg after both i.v. and oral administration. Elimination half-life, clearance and volume of distribution are considered to be dose-independent. Following repeated i.v. or oral administration, the AUC of pantoprazole was similar to a single dose.
Despite its relatively short elimination half-life of approximately 1 hour, the antisecretory effect increases during repeated once daily administration, demonstrating that the duration of action markedly exceeds the serum elimination half-life. This means that there is no direct correlation between the serum concentrations and the pharmacodynamic action.
Absorption:
Pantoprazole magnesium is absorbed rapidly following administration of a 40 mg enteric-coated tablet. Following an oral dose of 40 mg, mean maximum serum concentrations of approximately 1.3 μg/mL and 1.4 μg/mL are reached after about 2.5 and 6 hours under fasting and fed conditions respectively. The AUC is approximately 4 μg.h/mL. Time to reach maximum serum concentrations is slightly increased when the drug is given together with a high caloric breakfast. Taking into account the long duration of action of pantoprazole, which by far exceeds the time period over which serum concentrations are measurable, this observed variation in tmax is considered to be of no clinical importance.
Morning administration of pantoprazole sodium was significantly superior to evening dosing with regard to 24-hour intragastric pH, hence morning dosing should be recommended for the treatment of patients. Since the intake of the drug before a breakfast did not influence Cmax and AUC, which characterize rate and extent of absorption, no specific requirements for intake of pantoprazole in relation to breakfast are necessary. The absolute bioavailability of the pantoprazole sodium tablet is 77%.
Distribution:
Pantoprazole is 98% bound to serum proteins. Elimination half-life, clearance and volume of distribution are independent of the dose.
Metabolism:
Pantoprazole is almost completely metabolized in the liver. Studies with pantoprazole sodium in humans reveal no inhibition or activation of the cytochrome P450 (CYP 450) system of the liver.
Pantoprazole undergoes metabolic transformation in the liver. The main serum metabolites (M1-M3) are sulphate conjugates formed after demethylation at the pyridine moiety, the sulphoxide group being either retained (M2, main metabolite), or oxidized to a sulphone (M1), or reduced to a sulphide (M3). These metabolites also occur in the urine (main metabolite M2). Conjugates with glucuronic acid are also found in the urine.
Elimination:
Renal elimination represents the major route of excretion (about 82%) for the metabolites of pantoprazole, the remaining metabolites are excreted in feces. The main metabolite in both the serum and urine is desmethylpantoprazole as a sulphate conjugate. The half-life of the main metabolite (about 1.5 hours) is not much longer than that of pantoprazole (approximately 1 hour).
For combination therapy of pantoprazole with clarithromycin and amoxicillin or metronidazole, please refer to section 9.4 Drug-Drug Interactions.
Special Populations and Conditions
Pediatrics:
No data are available to Health Canada; therefore, Health Canada has not authorized an indication for pediatric use.
Geriatrics:
An increase in AUC (35%) and Cmax (22%) for pantoprazole occurs in elderly volunteers when compared to younger volunteers after 7 consecutive days oral dosing with pantoprazole sodium 40 mg. After a single oral dose of pantoprazole sodium 40 mg, an increase in AUC (43%) and Cmax (26%) occurs in elderly volunteers when compared to younger volunteers. No dose adjustment is recommended based on age. The daily dose in elderly patients, as a rule, should not exceed the recommended dosage regimens.
Hepatic Insufficiency:
The half-life increased to between 7 and 9 h, the AUC increased by a factor of 5 to 7, and the Cmax increased by a factor of 1.5 in patients with liver cirrhosis compared with healthy subjects following administration of 40 mg pantoprazole sodium. Similarly, following administration of a 20 mg dose, the AUC increased by a factor of 5.5 and the Cmax increased by a factor of 1.3 in patients with severe liver cirrhosis compared with healthy subjects. Considering the linear pharmacokinetics of pantoprazole sodium, there is an increase in AUC by a factor of 2.75 in patients with severe liver cirrhosis following administration of a 20 mg dose compared to healthy volunteers following administration of a 40 mg dose.
Renal Insufficiency:
In patients with severe renal impairment, pharmacokinetic parameters for pantoprazole sodium were similar to those of healthy subjects. No dosage adjustment is necessary in patients with renal impairment or in patients undergoing hemodialysis, as the difference in AUCs between patients who are dialyzed and those who are not is 4%.
STORAGE, STABILITY AND DISPOSAL
Store at 15°C to 30°C in the recommended packaging. Keep out of reach and sight of children.
SPECIAL HANDLING INSTRUCTIONS
No special handling instructions are required for this product.
PART II: SCIENTIFIC INFORMATION
PHARMACEUTICAL INFORMATION
Drug Substance
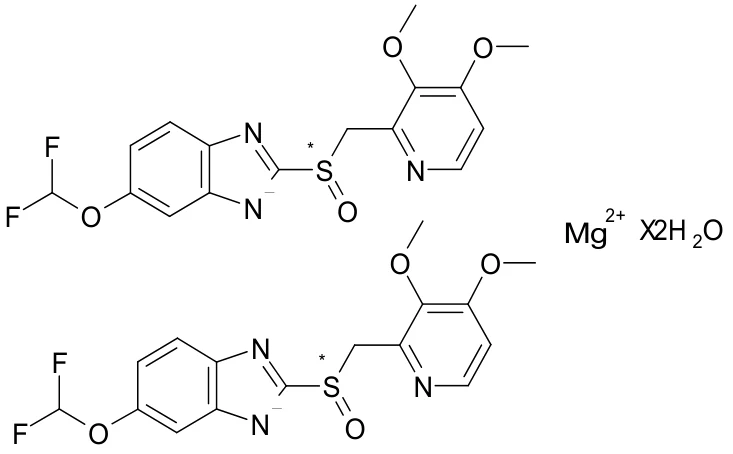
Proper name: Pantoprazole magnesium
Chemical name: magnesium bis [5-(difluoromethoxy)-2-[[(3,4-dimethoxy-2-pyridinyl) -methyl]-sulfiny1]-1-H-benzimidazolide] dihydrate
Molecular formula and molecular mass: C32H28F4MgN6O8S2 x 2H2O, 825.08 g/mol
Structural formula:
Physicochemical properties:
Physical description: White to beige powder
Solubilities in common solvents (e.g., water, alcohols, chloroform, acetone, dilute acids, etc.):
Solvent Concentration
Water (pH 8.24 - 8.74, 37°C) Cs = (3.39±0.50) x 10-4 Mol/l
Buffer (pH 6.83-6.92, 37°C) Cs = (5.99±0.18) x 10-4 Mol/l
Buffer pH 7.4 (37°C) Cs = (6.70±0.44) x 10-4 Mol/l
Buffer pH 11 (37°C) Cs = (9.98±0.46) x 10-4 Mol/l
Methanol (22-24°C) Cs = (3.58±0.04) x 10-2 Mol/l
Ethanol (22-24°C) Cs = (3.63±0.14) x 10-3 Mol/l
Acetone (22-24°C) Cs = (7.79±0.21) x 10-5 Mol/l
Acetonitrile (22-24°C) Cs = (3.46±0.27) x 10-5 Mol/l
N-hexane (22-24°C) Cs <1.54x10⁻⁷ Mol/l
pH and pKa values: The following pKa-values have been determined at 25°C, as follows:
Pka1 = 8.11 ± 0.02 (n = 7)
Pka2 = 3.77 ± 0.02 (n = 7)
Other: Partition coefficient in octanol / water:
LogD 7.4 = log [c(octanol) / c (H2O)] = 2.02 ± 0.01 (n = 3)
CLINICAL TRIALS
 Clinical Trials by Indication
Reduction of Gastric Acid Secretion
Healing of Gastro-Esophageal Reflux Disease
Table 11. Summary of patient demographics for clinical trials in healing of gastroesophageal reflux disease (GERD) in adult patients
| Study # | Study Design | Dosage, route of administration and duration | Study subjects (n) | Mean age (Range) | Sex |
|---|---|---|---|---|---|
| M3-323 (337/2003) | Randomized, double-blind, multicenter, parallel-group comparison | Pantoprazole magnesium: 40 mg, QD, Oral, 4-8 weeks Pantoprazole sodium: 40 mg, QD, Oral, 4-8 weeks | Total = 636 Pantoprazole-Mg: 322 Pantoprazole-Na: 314 | 18-84 | Male and Female |
Study Results: A double-blind, randomized, parallel group clinical study comparing 40 mg pantoprazole magnesium to 40 mg pantoprazole sodium was performed in 636 patients with GERD grades 1 – 3 (Savary-Miller classification, modified by Siewert; Table 11). The primary variable was endoscopically confirmed healing of reflux esophagitis after 8 weeks of treatment with either pantoprazole magnesium or pantoprazole sodium. After 4 weeks of treatment, the healing rates for pantoprazole magnesium and pantoprazole sodium in the ITT population were 72.7% and 66.2% respectively (Table 12). Pantoprazole magnesium 40 mg once daily (QD) was proven to be comparable to pantoprazole sodium 40 mg QD with respect to endoscopic healing after 8 weeks of treatment (with healing rates for the ITT population of 87.3% and 85.0% respectively; Table 13). This represents a statistically significant difference.
Table 12. Healing rates (%) after 4 weeks with reflux esophagitis
| Population | Pantoprazole-Mg | Pantoprazole-Na | Difference | 95% CI of difference |
ITT1-population (N) Healing rate (%) (95% confidence interval) | N = 322 patients 72.7 (67.5; 77.5) | N = 314 patients 66.2 (60.7; 71.5) | 6.4 | (0.43; 12.43) |
PP2-population (N) Healing rate (%) (95% confidence interval) | N = 271 patients 77.9 (72.4; 82.7) | N = 261 patients 71.6 (65.8; 77.0) | 6.2 | (0.03; 12.40) |
1ITT = Intention to Treat
2PP = Per Protocol
Non-inferiority determined when the confidence interval for the difference between the two healing rates is completely above the non-inferiority margin of -10%.
Table 13. Healing rates (%) after 8 weeks with reflux esophagitis
| Population | Pantoprazole-Mg | Pantoprazole-Na | Difference | 95% CI of difference |
| ITT1-population (N) Healing rate (%) (95% confidence interval) | N = 322 patients 87.3 (83.1; 90.7) | N = 314 patients 85.0 (80.6; 88.8) | 2.2 | (-2.3; 6.7) |
| PP2-population (N) Healing rate (%) (95% confidence interval) | N = 271 patients 91.9 (88.0; 94.8) | N = 261 patients 91.2 (87.1, 94.3) | 0.7 | (-3.3; 4.7) |
1ITT = Intention to Treat
2PP = Per Protocol
Non-inferiority determined when the confidence interval for the difference between the two healing rates is completely above the non-inferiority margin of -10%.
Symptomatic Gastro-Esophageal Reflux Disease
Table 14. Summary of patient demographics for clinical trials in symptomatic gastro-esophageal reflux disease in adult patients
| Study # | Study Design | Dosage, route of administration and duration | Study subjects (n) | Mean age (Range) | Sex |
|---|---|---|---|---|---|
| 3001A1-300-US | Randomized, double-blind, multicenter, placebo-controlled, parallel-group comparative study | Pantoprazole or Placebo: 10, 20 or 40 mg, QD, Oral, 4-8 weeks | 538 | 18 - 82 | Male and Female |
| 3001A1-301-US | Pantoprazole: 20 or 40 mg, QD, Oral, 4-8 weeks Nizatidine: 150 mg, BID, Oral, 4-8 weeks | 215 | 18-79 | Male and Female |
Study Results: In a US placebo-controlled study involving 538 patients, a significantly greater proportion of patients taking pantoprazole sodium 40 mg experienced complete relief of daytime and nighttime heartburn and the absence of regurgitation starting from the first day of treatment compared with placebo. Patients taking pantoprazole sodium consumed significantly fewer antacid tablets per day than those taking placebo.
In a second US study involving 215 patients, a significantly greater proportion of the patients in the pantoprazole sodium treatment groups experienced complete relief of nighttime heartburn and regurgitation starting on the first day and of daytime heartburn on the second day compared with those taking nizatidine 150 mg twice daily. Patients taking pantoprazole sodium consumed significantly fewer antacid tablets per day than those taking nizatidine.
Based upon the similar inhibition of acid secretion and effect on intragastric pH as pantoprazole sodium, TECTA® is expected to have similar daytime and night-time relief of symptoms.
Helicobacter pylori (H. pylori) Associated Duodenal Ulcer
Table 15. Summary of patient demographics for clinical trials in Helicobacter pylori associated duodenal ulcer in adult patients
| Study # | Study Design | Dosage, route of administration and duration | Study subjects (n) | Mean age (Range) | Sex |
|---|---|---|---|---|---|
| Triple combination therapy | Randomized, double-blind, multicenter, parallel group study | Study 1 & 2: Pantoprazole sodium 40 mg + clarithromycin 500 mg + metronidazole 500 mg, BID, Oral, 1 week Study 2, 3 & 4: Pantoprazole sodium 40 mg + amoxicillin 1000 mg + clarithromycin 500 mg, BID, Oral, 1 week | Study 1 = 213; Study 2 = 283; Study 3 = 62; Study 4 = 57 | 20-95 | Male and Female |
Study Results:
Table 16. Results of studies in patients with active duodenal ulcer who were H. pylori positive
| Treatment | Eradication Rate (ITT + kpa analysis) | 95% CI | Ulcer Healing Rate after therapy cessation (MITT analysis) | 95% CI | |
Pantoprazole sodium 40 mg + clarithromycin 500 mg + metronidazole 500 mg, all twice daily for 1 week (PCM) | Study 1 | 83% | 75-90% | 88% | 80-93% |
| Study 2 | 96% | 91-98% | Not assessed | ||
Pantoprazole sodium 40 mg + amoxicillin 1000 mg + clarithromycin 500 mg, all twice daily for 1 week (PAC) | Study 2 | 93% | 88-97% | Not assessed | |
| Study 3 | 86% | 68-96% | 88% | 72-97% | |
| Study 4 | 86% | 74-94% | 92% | 82-97% |
ITT + kpa: Patients who were H. pylori positive at the initial examination and had complete and valid results for the requisite (based on the study) number of tests at the appropriate follow-up visit. In study 1, 3 of 4 H. pylori tests must be complete and valid.
Study 1: Patients with active duodenal ulcer, were assessed for H. pylori status by UBT, histology, culture and rapid urease, n=213 (ITT + kpa)
Study 2: Patients with active duodenal ulcer, were assessed for H. pylori status by UBT and rapid urease pre-treatment and by UBT post-treatment, n=283 (ITT + kpa)
Study 3: Patients with active duodenal ulcer, were assessed for H. pylori status by rapid urease and UBT pre-treatment and by UBT and histology post-treatment, n=62 (ITT + kpa)
Study 4: Patients with active duodenal ulcer, were assessed for H. pylori status by rapid urease, culture and histology pre-treatment and culture and histology post-treatment, n=57 (ITT + kpa)
Relapse of Reflux Esophagitis
Table 17. Summary of patient demographics for clinical trials in prevention of relapse of reflux esophagitis in adult patients
| Study # | Study Design | Dosage, route of administration and duration | Study subjects (n) | Mean age (Range) | Sex |
|---|---|---|---|---|---|
| 3001A1-302-US | Randomized, double-blind, parallel-group, active-controlled | Pantoprazole 20 mg QD; Pantoprazole 40 mg QD; Ranitidine 150 mg BID Oral 12 months | 349 | 21-81 | Male and Female |
| 3001A1-303-US | Randomized, double-blind, parallel-group, active-controlled | Pantoprazole 20 mg QD; Pantoprazole 40 mg QD; Ranitidine 150 mg BID Oral 12 months | 371 | 18-81 | Male and Female |
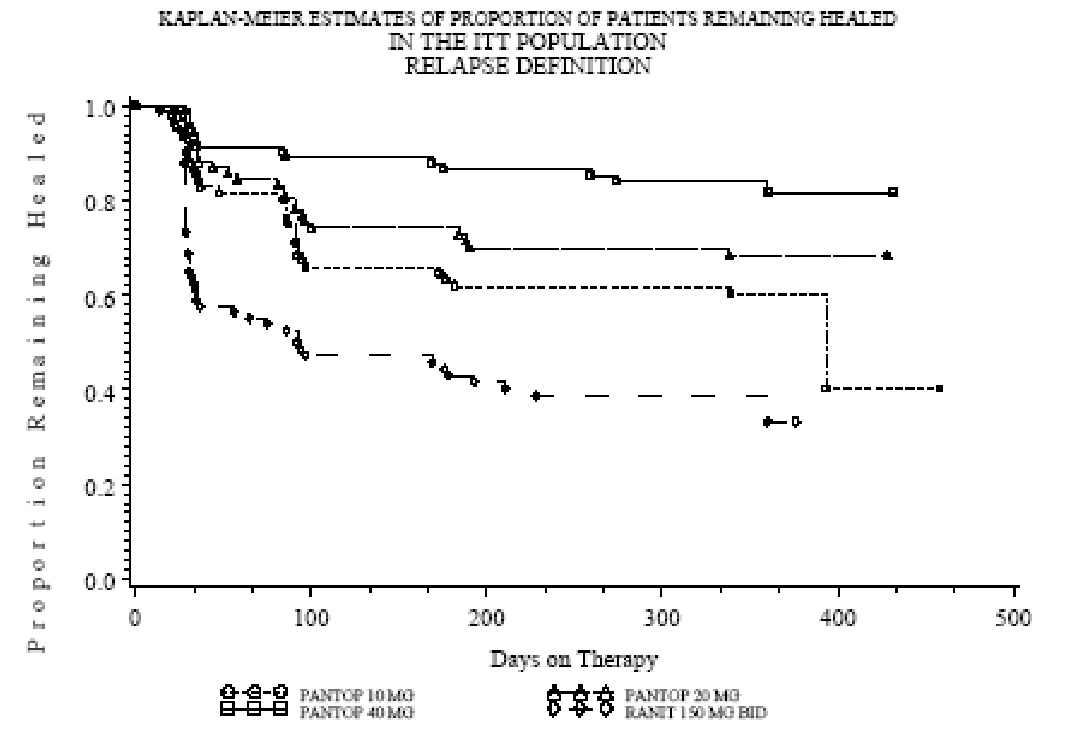
Study Results: The long-term maintenance of healing of erosive esophagitis was assessed in two U.S. randomised, double-blind, parallel-group, active controlled studies. Eligible patients in both studies had a recent history of grade II or III (Hetzel-Dent) erosive esophagitis, and endoscopically demonstrated healing. Both studies used as the primary endpoint endoscopically demonstrated recurrence (assessed at month 1, 3, 6 and 12) of erosive esophagitis ('relapse'). Gelusil antacid tablets were to be taken as needed for symptomatic relief after 5 or more minutes of retrosternal pain, acid regurgitation, or dysphagia, but not within 1 hour before or after taking study medication. Ad hoc endoscopies were performed when symptoms of GERD occurred for more than 3 consecutive days. As the primary analysis Kaplan Meier’s method was performed, whereas the discrete analysis was secondary. In the U.S. studies, there were a limited number of H. pylori positive patients. Results for this sub-group are therefore qualitative only.
In the US studies, the results of Kaplan-Meier’s analyses showed that the cumulative proportion of relapse over time was dose-related for the pantoprazole treatment groups. The cumulative proportion of relapse at 12 months for patients treated with pantoprazole 20 mg and pantoprazole 40 mg exhibited a statistically significant difference in the pooled data (p-value = 0.001) and in the data of one of the studies (3001A1-302-US: p-value = 0.012, 3001A1-303-US p-value=0.052) (p-values adjusted for pairwise comparison).
Figure 1. Kaplan-Meier plot; 3001A1-302-US
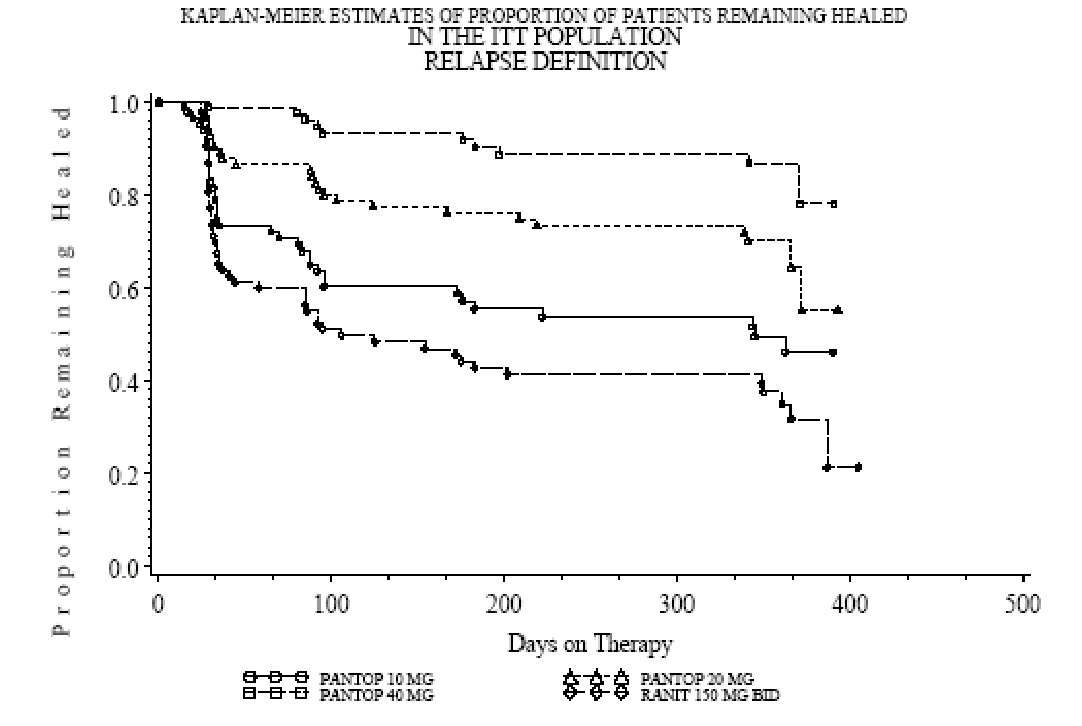
Figure 2. Kaplan-Meier plot; 3001A1-303-US
In the discrete analysis of the pooled results of the two U.S. studies, 40 mg was significantly (p-value = 0.004) more effective in the maintenance of healed erosive esophagitis compared to 20 mg (Table 18).
Table 18. Long-term maintenance of healing of erosive esophagitis: Proportion of patients who relapse in individual studies and pooled studies at 12 months. U.S. Studies
Pantoprazole 20 mg n/N (%) | Pantoprazole 40 mg n/N (%) | Ranitidine 150 mg n/N (%) | ||||
|---|---|---|---|---|---|---|
| Study 3001A1-302-US | ||||||
Month 1 Month 3 Month 6 Month 12 | 11/86 (12.8)* 17/77 (22.1)* 21/77 (27.3)* 25/75 (33.3)* | 1/78 (1.3)* 5/76 (6.6)* 8/70 (11.4)* 10/64 (15.6)* a | 32/84 (38.1) 41/81 (50.6) 47/77 (61.0) 52/76 (68.4) | |||
| Study 3001A1-303-US | ||||||
Month 1 Month 3 Month 6 Month 12 | 11/87 (12.6)* 21/80 (26.3)* 24/75 (32.0)* 25/73 (34.2)* | 8/93 (8.6)* 10/88 (11.4)* 12/85 (14.1)* 15/78 (19.2)* | 37/92 (40.2) 45/83 (54.2) 51/79 (64.6) 52/78 (66.7) | |||
| Pooled data | ||||||
| Month 12 | 50/148 (33.8) * | 25/142 (17.6) * a | 104/154 (67.5) | |||
*Statistically significant between treatment and ranitidine at 0.05 level; a Statistically significant between pantoprazole 40 mg and 20 mg with adjusted p-value (Holm procedure). Mean age 302-US 49.2 years, 303-US 48.95 years, 302-US: 28% female / 72% male 303-US: 38% female / 62% male, 302-US: 3.9 % black, 4.1 % Hispanic, <1% Asian, 91% white, <1% other, US-303: 6.4 % black, 6.4 % Hispanic, <1% Asian, 86% white, <1% other, US-302: 85% H. pylori negative, 15% H. pylori positive, US-303: 88% H. pylori negative, 12% H. pylori positive.
MICROBIOLOGY
In Vivo Studies
Female mice were infected with Helicobacter felis on Days 1, 3, and 5 by gavage with 108 - 109 bacteria per animal. Starting on Day 8, the mice were treated three times daily with placebo or active drug (pantoprazole sodium and/or amoxicillin, clarithromycin, tetracycline) for four days. One day after the last treatment, the mice were sacrificed and a biopsy of the antrum was subjected to a urease test, with only those tests showing a dark violet colour considered to contain urease-positive Helicobacter.
Table 19. Doses of the active agents, the number of infected animals per group, and resulting elimination rates for the H. felis infection
| Active Dosing Groups | Elimination Rates |
| Pantoprazole sodium 100 mg/kg tid (n=10) | 0% |
| Amoxicillin 0.5 mg/kg tid (n = 10) | 40% |
| Amoxicillin 3.0 mg/kg tid (n = 10 ) | 100% |
| Clarithromycin 0.5 mg/kg tid (n = 10) | 10% |
| Clarithromycin 3.0 mg/kg tid (n = 10) | 70% |
| Tetracycline 3.0 mg/kg tid (n = 20) | 55% |
| Tetracycline 15.0 mg/kg tid (n = 10) | 90% |
| Pantoprazole sodium 100 mg/kg tid + amoxicillin 0.5 mg/kg tid (n = 10) | 100% |
| Pantoprazole sodium 100 mg/kg tid + clarithromycin 0.5 mg/kg tid (n = 10) | 90% |
| Pantoprazole sodium 100 mg/kg tid + tetracycline 3.0 mg/kg tid (n = 20) | 80% |
In the infected, placebo dosed positive control group, 24 of the 25 mice had positive urease tests, while the negative control group (not infected, placebo dosed) all had negative urease tests.
Pantoprazole sodium alone was without effect on Helicobacter felis infection, while in combination therapy with the antibiotics, pantoprazole sodium had a potentiating effect on the elimination rate of Helicobacter felis infection. The results show a potentiation by a factor of about six, i.e., pantoprazole sodium plus the low dose antibiotic achieved an infection elimination rate greater than or approximately equal to the higher dose of antibiotic given alone, which was dosed at five to six times higher than the low dose.
NON-CLINICAL TOXICOLOGY
General Toxicology:
Acute Toxicity
In single dose rodent (rat and mice) studies with pantoprazole magnesium, no toxic effects were noted under any of the doses administered (100, 300, 1000 mg/kg).
In acute toxicity studies in mice, the mean lethal dose (LD50) values for pantoprazole sodium were found to be greater than 370 mg/kg bodyweight for i.v. administration and over 700 mg/kg bodyweight for oral administration.
In the rat, the corresponding values were greater than 240 mg/kg for i.v. administration and greater than 900 mg/kg for oral administration.
In general, therefore, higher doses of pantoprazole magnesium than of the sodium salt were tolerated by both rats and mice in single dose studies.
Table 20. Acute toxicity studies with pantoprazole sodium
| Species | Route | Sex | Lethal dose mg/kg |
| Mouse | p.o. | M | >945 |
| F | 707 | ||
| i.v. | M | 377 | |
| F | 374 | ||
| Rat | p.o. | M | 1191 |
| F | 919 | ||
| i.v. | M | 293 | |
| F | 242 | ||
| Dog | p.o. | M/F | 266-887 |
| i.v. | F/F | 133-266 |
Doses in terms of the free compound
The symptoms seen after lethal oral or i.v. doses were similar in rats and mice: the animals displayed ataxia, reduced activity, hypothermia and prostration. Surviving animals recovered uneventfully. Salivation, tremor, lethargy, prostration and coma were seen in dogs at lethal oral doses, with death occurring on the following day. Ataxia, tremor and a prone position were noted at sublethal oral and i.v. doses, but the survivors recovered quickly and appeared fully normal after the 2-week observation period.
Chronic Toxicity
Pantoprazole magnesium was administered orally once daily to groups of 10 male/10 female rats at doses of 0, 50 and 200 mg/kg/day for 4 weeks. As a comparison, pantoprazole sodium was administered once daily to groups of 10 male/10 female rats at the same doses (50 and 200 mg/kg/day). For toxicokinetic analysis, further groups of 2 males/2 females or 6 males/6 females were treated with pantoprazole magnesium at 0, 50 or 200 mg/kg/day or with pantoprazole sodium at 50 or 200 mg/kg/day, with blood samples taken on Day 1, 7 and in the 4th test week.
No qualitative or quantitative differences in the pattern of toxic effects were observed in rats after repeated administration of equal doses of pantoprazole as a magnesium or sodium salt. No remarkable differences in the toxicokinetic characteristics between the two salt forms were detected in rats.
Daily oral doses of pantoprazole sodium in 1- and 6-month SD rat repeated-dose studies were 1, 5, 20, and 500 mg/kg and 0.8, 4, 16 and 320 mg/kg, respectively; doses for a 1 month rat i.v. study were 1, 5, and 30 mg/kg.
A 12-month toxicity study of pantoprazole sodium in SD rats was conducted using daily oral doses of 5, 50, and 300 mg/kg. Daily oral doses in 1- and 6 month (beagle) dog studies were 7.5, 15, 30, and 100 mg/kg and 5, 15, 30, and 60 mg/kg respectively. In a 12-month oral study in dogs, 2.5, 15, and 60 mg/kg were administered daily.
Hypergastrinemia was dose-related and was observed at all doses investigated in the studies mentioned above, but was reversible upon cessation of treatment. Drug-related effects on the stomach included increased stomach weights and morphologic changes of the mucosa. In the 6-month rat study, increased stomach weight and some cellular changes were detected at all doses. In the 1-month rat study, gastric changes were detected at 5 mg/kg but not at 1 mg/kg. In dogs, increased stomach weight was observed at all doses studied. There were no gastric cellular changes detected at oral doses of 7.5 or 5 mg/kg in the 1- and 6-month dog studies, respectively. In both species, most gastric effects were reversible after a 4- or 8-week recovery period. Hypergastinemia and gastric changes were considered to be the consequence of the pharmacological action of the compound, namely prolonged and profound inhibition of acid secretion.
Increased liver weight in the rat experiments was considered to be a consequence of the induction of hepatic drug metabolizing systems and was found to be associated with centrilobular hepatocellular hypertrophy at 320 mg/kg in the 6-month study and at 50 and 300 mg/kg after 12 months of treatment. Increased liver weights were also detected at a dose of 16 mg/kg in male rats in the 6-month study and at 500 mg/kg, but not 20 mg/kg, in the 1-month study. Increased liver weight was noted in male dogs of all dose groups in the 1-month study, though only at 100 mg/kg in females on the same study. Both males and females had increased liver weights after 6 months administration of 30 or 60 mg/kg, but not of 15 mg/kg. In the 12-month study, liver weights were increased only in the female dogs dosed with 60 mg/kg. There were no hepatic lesions that correlated with increased liver weight in the dog studies. In dogs, the increase in liver weight was attributed to an activation of hepatic drug metabolizing systems as mentioned for rats.
Thyroid activation in animal experiments is due to the rapid metabolization of thyroid hormones in the liver and has been described in a similar form for other drugs. Thyroid weights were increased in both sexes at 500 mg/kg in the 1-month rat study and at 320 mg/kg in the rat 6-month study. Thyroid follicular cell hypertrophy was noted in females at these doses, in rats treated with 50 and 300 mg/kg in the 12 month study and also in a few females at 16 mg/kg in the 6 month study. There were no thyroid effects in rats at or below an oral dose of 5 mg/kg even after 1 year. In the dog, no effects were seen on the thyroid after 4 weeks. Only slight, but not dose-dependent, increases in thyroid weights were seen after 6 months, but no changes were observed histologically. In the 12 month study, the relative thyroid weights in the 60 mg/kg group were only slightly higher than those of the control dogs, and changes were detected histologically in only a few animals under 15 and 60 mg/kg. In both species, changes were reversible.
Increased serum cholesterol values were noted in all groups in the 6- and 12 month dog studies and in all groups in the 12 month rat study. The increases were slight and were reversible after cessation of treatment.
In dog studies, oral doses of pantoprazole sodium of 15 mg/kg or above caused a transient pulmonary edema in a proportion of naive dogs during the first week of drug administration. Pulmonary edema caused death in a few dogs after repeated oral doses of 15 mg/kg or above. There is strong evidence that the pulmonary toxicity is due to a thiol metabolite which does not occur in man. No evidence of pulmonary edema was detected in dogs at an oral dose of 7.5 mg/kg nor at 60 mg/kg when administered daily for 6 or 12 months after a 1 week dose escalation phase.
In a four week oral toxicity study, Beagle dogs were given daily oral doses of encapsulated commercial products including pantoprazole sodium, clarithromycin, metronidazole, and amoxicillin. Groups of three male and three female dogs received the following daily doses of pantoprazole and/or antibiotics:
Group 1 - pantoprazole sodium 16 mg/kg
Group 2 - clarithromycin 75 mg/kg + metronidazole 50 mg/kg
Group 3 - pantoprazole sodium 16 mg/kg + amoxicillin 120 mg/kg + metronidazole 50 mg/kg
Group 4 - pantoprazole sodium 16 mg/kg + amoxicillin 120 mg/kg + clarithromycin 50 mg/kg
Group 5 - pantoprazole sodium 16 mg/kg + clarithromycin 75 mg/kg + metronidazole 50 mg/kg
Histomorphological investigations indicated that treatment with clarithromycin and metronidazole alone (Group 2) induced an atrophic gastritis, which was not seen when these products were given concomitantly with pantoprazole. In Group 5, however, the total mucosal appearance was diagnosed as quite normal, and the height of the mucosa was not decreased. In the recovery dogs, the mucosae were also judged to be normal.
In all groups dosed with clarithromycin (Groups 2, 4, 5), inflammation and hyperplasia of the gallbladder, together with degeneration of the renal papilla were noted. These changes were absent from the Group 5 recovery dogs (only tubular swelling, increased tubular pigment noted), indicating reversibility. A slight centrilobular hypertrophy was observed in the liver of most animals.
In dogs which had positive 13C-urea breath tests prior to treatment, the Helicobacter-like organism responsible was eliminated in Groups 2 through 5, and remained eradicated in the Group 5 recovery animals.
Based on the results of this study, it was concluded that no additional toxic effects were observed during concomitant administration of different antibiotics with pantoprazole sodium.
Carcinogenicity:
Three carcinogenicity studies had been conducted with pantoprazole sodium:
- A 24 month oral study was conducted at doses of 0.5, 5, 50 and 200 mg/kg/day in SD rat.
- A 24 month oral study was conducted at doses of 5, 15 and 50 mg/kg/day in Fischer-344 rat.
- A 24 month oral study was conducted at doses of 5, 25 and 150 mg/kg/day in B6C3F1 mouse.
Pantoprazole sodium, dissolved in distilled water, was administered once a day by oral gavage to groups of 50 male and 50 female B6C3F1 mice at doses of 5, 25, or 150 mg/kg. An identical control group was dosed with distilled water (pH 10), while a second identical control group received no treatment at all. In the first rat study, pantoprazole sodium was administered once a day by oral gavage to groups of 70 male and 70 female SD rats at doses of 0.5, 5, 50, and 200 mg/kg. A control group of 70 males and 70 females received the vehicle. In the second rat study, pantoprazole sodium was administered once a day by oral gavage to groups of 50 male and 50 female Fischer-344 rats at doses of 5, 15, and 50 mg/kg. A control group of 50 males and 50 females received the vehicle, while another group remained untreated.
In the first 2 year carcinogenicity study in rats, which corresponds to a lifetime treatment for rats, neuroendocrine neoplasms were found in the stomach at doses of 50 mg/kg/day and above in males and at 0.5 mg/kg/day and above in females. Tumor formation occurred late in the life of the animals (only after 17 months treatment), whereas no tumors were found in rats treated with an even higher dose for 1 year. The mechanism leading to the formation of gastric carcinoids by substituted benzimidazoles has been carefully investigated, and it is considered to be due to high levels of serum gastrin observed in the rat during chronic treatment. In the second rat carcinogenicity study, neuroendocrine cell tumors in the stomach were found in all treated female groups and in the male 15 and 50 mg/kg groups. No metastases from any gastric neuroendocrine cell tumours were detected.
ECL-cell neoplasms were not observed in either the carcinogenicity study in the mouse (24 months) or in the chronic studies in the dog. In clinical studies, with treatment of 40 - 80 mg of pantoprazole sodium for 1 year, ECL-cell density remained almost unchanged.
Microscopy of the rat (first carcinogenicity study) and mouse tissues gave evidence for an increase in liver tumors. In the rat experiment, the incidence of benign liver tumors in the 50 and 200 mg/kg groups and the incidence of hepatocellular carcinoma was increased in the males and females of the 200 mg/kg group. There was a slightly higher incidence of hepatocellular adenomas and carcinomas in the female mice of the 150 mg/kg group than in either of the 2 control groups. Other changes in the liver morphology were present as well. Centrilobular hepatocellular hypertrophy increased in incidence and severity with increasing dose, and hepatocellular necrosis was increased in the highest dose in the rat studies and in the mouse study. Hepatocellular tumors are common in mice, and the incidence found for the female 150 mg/kg group was within historical control ranges for this strain. The liver tumor incidences in rats treated with 50 mg/kg and in the male rats treated with 200 mg/kg were also within historical control incidences for the rat. These tumors occurred late in the life of the animals and were primarily benign. The nongenotoxic mechanism of rodent liver tumor formation after prolonged treatment with pantoprazole sodium is associated with enzyme induction leading to hepatomegaly and centrilobular hypertrophy and is characterized by tumor induction in low incidences at high doses only. As pantoprazole acts in a similar fashion to phenobarbital, causing reversible centrilobular hepatocellular hypertrophy and enzyme induction in short-term studies, it is probable that the mechanism of action for induction of the liver tumors seen in long-term rodent studies is also the same. Hepatocellular tumors at high doses in rodents are not indicative of human carcinogenic risk.
A slight increase in neoplastic changes of the thyroid was observed in rats receiving pantoprazole sodium at 200 mg/kg/day. The incidences of these tumours were within the historical control ranges for this rat strain. No thyroid neoplasms were observed in the 12-month study. The no-effect dose for both male and female rats is 50 mg/kg, which is 100 times the human dose (i.e., 40 mg dose). The effect of pantoprazole sodium on the thyroid is secondary to the effects on liver enzyme induction, which lead to enhanced metabolism of thyroid hormones in the liver. As a consequence, increased TSH is produced, which has a trophic effect on the thyroid gland. Clinical studies have demonstrated that neither liver enzyme induction nor changes in thyroid hormonal parameters occur in man after therapeutic doses of pantoprazole sodium.
Tumors induced in rats and mice by pantoprazole sodium were the result of nongenotoxic mechanisms which are not relevant to humans. Tumors were induced in rodents at dosages that provide higher exposure than with human therapeutic use. Based on kinetic data, the exposure to pantoprazole sodium in rats receiving 200 mg/kg was 22.5 times higher than that found in humans receiving 40 mg oral doses. In mice receiving 150 mg/kg, exposure to pantoprazole sodium was 2.5 times higher than that in humans.
Genotoxicity:
Pantoprazole sodium was studied in several mutagenicity studies: Pantoprazole sodium was found negative in the Ames test, in vivo chromosome aberration assay in rat bone marrow, a mouse lymphoma test, two gene mutation tests in Chinese hamster ovary cells in vitro, and two micronucleus tests in mice in vivo. Pantoprazole was found positive in three of four chromosome aberration assays in human lymphocytes in vitro. The in vitro tests were conducted both in the presence and absence of metabolic activation. In addition, the potential of pantoprazole sodium to induce DNA repair synthesis was tested negative in an in vitro assay using rat hepatocytes. In addition, a rat liver DNA covalent binding assay showed no biologically relevant binding of pantoprazole to DNA.
In addition, two in vitro cell transformation assays using different cell types were performed to aid in the interpretation of the rodent carcinogenicity studies; in neither test did pantoprazole sodium enhance the morphologic transformation of the cell types used.
A bacterial mutation assay conducted with the degradation product B8810-044, gave no indication of a mutagenic potential.
Reproductive and Developmental Toxicology:
Pantoprazole sodium was not teratogenic to rats or rabbits at doses up to 450 and 40 mg/kg/day (gavage), 20 and 15 mg/kg/day (i.v. injection), respectively.
Treatment of male rats with pantoprazole sodium up to 500 mg/kg p.o. for 127 days did not affect fertility. Treatment of pregnant rats induced dose-dependent fetotoxic effects: increased pre- and postnatal deaths (450 mg/kg/day), reduced fetal weight and delayed skeletal ossification (150 mg/kg/day), and reduced pup weight (15 mg/kg/day). These results may be explained by maternal toxicity of pantoprazole at high dose and/or placental transfer of pantoprazole.
Penetration of the placenta was investigated in the rat and was found to increase with advanced gestation. As a result, concentration of pantoprazole in the fetus is increased shortly before birth regardless of the route of administration.
In a peri-postnatal rat reproduction study designed to assess bone development, signs of offspring toxicity (mortality, lower mean body weight, lower mean body weight gain and reduced bone growth) were observed at exposures (Cmax) approximately 2x the human clinical exposure. By the end of the recovery phase, bone parameters were similar across groups and body weights were also trending toward reversibility after a drug-free recovery period. The increased mortality has only been reported in pre-weaning rat pups (up to 21 days age) which is estimated to correspond to infants up to the age of 2 years old. The relevance of this finding to the paediatric population is unclear. A previous peri-postnatal study in rats at slightly lower doses found no adverse effects at 3 mg/kg compared with a low dose of 5 mg/kg in this study. Investigations revealed no evidence of impaired fertility or teratogenic effects.
In humans, there is no experience with the use of pantoprazole during pregnancy.
Non-Clinical Pharmacodynamics
In vivo, pantoprazole sodium produced marked and long-lasting inhibition of basal and stimulated gastric acid secretion with median effective dose (ED50) values ranging from 0.2 -2.4 mg/kg in rats and dogs. In addition to the administration of single doses, pantoprazole sodium has been tested upon repeated oral administration (e.g. during 24-h pH-metry in dogs performed under pentagastrin stimulation). While a dose of 1.2 mg/kg did not significantly elevate pH on Day 1, pH rose to values between 4 and 7 after a 5-day dosing regimen. This effect was no longer observed 18 hours after the last drug administration. In various gastric ulcer models in the rat, pantoprazole sodium showed antiulcer activity.
In parallel to the profound inhibition of gastric acid secretion, pantoprazole sodium induced a dose-dependent increase in serum gastrin levels up to values above 1000 pg/mL from a control level of about 100 pg/mL. As a consequence of persisting hypergastrinemia in rats after high doses of pantoprazole sodium, hyperplastic changes were observed in the fundic mucosa with an increased density of enterochromaffin-like (ECL) cells. These changes were reversible during drug-free recovery periods.
In a battery of standard high-dose pharmacology tests, no influence of pantoprazole sodium was detected on the central and peripheral nervous system. In conscious dogs as well as anaesthetized cats receiving single i.v. doses up to 10 mg/kg pantoprazole sodium, no consistent changes with respect to respiratory rate, ECG, EEG, blood pressure and heart rate were observed. Higher doses led to modest and transient reductions in blood pressure and variable changes in heart rate. No influence of pantoprazole sodium was found on renal function and on autonomic functions, such as pancreatic and bile secretion, gastrointestinal motility and body temperature.
No consistent changes in the effects of ethanol, pentobarbitone, or hexobarbitone were induced by pantoprazole sodium; only doses over 300 mg/kg prolonged the effects of diazepam.
Non-Clinical Pharmacokinetics
The pharmacokinetic characteristics of pantoprazole sodium (40 mg) and pantoprazole magnesium (40 mg) tablets were compared in a study in dogs. Male beagle dogs received a single oral dose in the form of uncoated tablets of either drug and blood samples were taken before and after administration. A sodium bicarbonate solution was administered together with the tablets to prevent degradation of pantoprazole in the stomach.
The ratio of the AUCs of the 40 mg pantoprazole magnesium tablet to the 40 mg pantoprazole sodium tablet was 86% and the corresponding value for Cmax was 62%. Thus, when equal doses were administered, the systemic exposure to pantoprazole was lower after administration of the magnesium than after the sodium salt. The terminal half-life (t1/2) of pantoprazole magnesium 40 mg was longer by approximately 23% compared to that of pantoprazole sodium. No difference in tmax between the two forms of pantoprazole was apparent.
Absorption and Distribution:
Pantoprazole sodium is absorbed rapidly in both rat and dog. Peak plasma levels are attained within 15 to 20 minutes in the rat and after about 1 hour in the dog. Oral bioavailability is 33% in the rat and 49% in the dog. Following absorption, autoradiography and quantitative tissue distribution experiments have shown that pantoprazole is rapidly distributed to extravascular sites. Following administration of pantoprazole sodium, distribution of radioactivity in the blood and most organs is found to be uniform initially. After 16 hours, radiolabelled pantoprazole is predominantly detected in the stomach wall. After 48 hours, all the administered radioactivity is found to have been excreted. Penetration of the blood-brain barrier by radiolabelled pantoprazole is very low. Protein binding in the rat and dog is 95% and 86%, respectively.
Metabolism and Elimination:
Pantoprazole is extensively metabolized. Oxidations and reductions at different sites of the molecule, together with Phase II reactions (sulfation and glucuronidation) and combinations thereof result in the formation of various metabolites. In rats and dogs, 29-33% of a pantoprazole sodium dose is excreted as urinary metabolites, and the remainder as biliary/fecal metabolites. Almost no parent compound can be found in the excreta.
Mammoglandular passage and transplacental transport has been investigated in the rat using radiolabelled pantoprazole sodium. A maximum of 0.23% of the administered dose is excreted in the milk. Radioactivity penetrates the placenta with 0.1-0.2% of the dose /g fetal tissue on the first day after oral administration.