


Product Monograph - Dimenhydrinate Injection USP (Hikma Canada)
SUMMARY PRODUCT INFORMATION
| Product | Route of Administration | Dosage Form / Strength | Non-medicinal Ingredients |
| Dimenhydrinate Injection USP | Intramuscular injection (or IV administration if diluted) | Sterile solution / 50 mg/mL 1 mL single use ampoules | 50% propylene glycol, water for injection, and hydrochloric acid for pH adjustment |
| Dimenhydrinate Injection USP | Intramuscular injection (or IV administration if diluted) | Sterile solution / 50 mg/mL (250 mg/5 mL) 5 mL multidose vials | 50% propylene glycol, water for injection, hydrochloric acid for pH adjustment, and methylparaben (as sodium methylparaben) and propylparaben (as sodium propylparaben) as preservatives |
INDICATIONS AND CLINICAL USE
Dimenhydrinate Injection USP is indicated for use in the prevention and relief of nausea, vomiting and/or vertigo. These symptoms may be associated with clinical situations such as motion sickness, radiation sickness, postoperative recovery, drug-induced nausea and vomiting, Menière’s disease and other labyrinthine disturbances. Parenteral therapy is available when oral or rectal therapy is inappropriate.
Geriatrics (over 65 years of age)
See WARNINGS AND PRECAUTIONS —Special Populations, Geriatrics.
Pediatrics (under 2 years of age)
The safety and efficacy of Dimenhydrinate Injection USP in children under the age of 2 have not been established. Dimenhydrinate Injection USP should not be used in this population (see CONTRAINDICATIONS and WARNINGS AND PRECAUTIONS —Special Populations, Pediatrics).
CONTRAINDICATIONS
- Patients who are hypersensitive to dimenhydrinate or its components (diphenhydramine or 8- chlorotheophylline) or to any ingredient in the formulations or component of the container. For a complete listing, see DOSAGE FORMS, COMPOSITION AND PACKAGING
During or within two weeks following therapy with a monoamine oxidase inhibitor (see
DRUG INTERACTIONS, Drugs with Anticholinergic Effects)
- Patients with glaucoma (narrow angle)
- Patients with chronic lung disease
- Patients with prostatic hypertrophy
- Patients under 2 years of age.
WARNINGS AND PRECAUTIONS
General
Dimenhydrinate Injection USP contains 50% (v/v) propylene glycol and is for intramuscular injection only. In exceptional circumstances, if the product is required for intravenous use, it must be diluted at least 1:10 with a compatible physiological solution such as sterile saline or 5% dextrose in water, to prevent propylene glycol-associated cardiogenic shock (see DOSAGE AND ADMINISTRATION, Dosing Considerations).
Dimenhydrinate Injection USP in 5 mL multidose vials contains the preservatives methylparaben and propylparaben. They are known to be associated with hypersensitivity in single or repeated uses.
The anticholinergic effects of the drug should be considered when administering dimenhydrinate to patients with conditions that might be aggravated by anticholinergic therapy (e.g. angle-closure glaucoma, enlargement of the prostate gland). These patients should be closely monitored during therapy with dimenhydrinate.
Avoid using dimenhydrinate within 14 days of MAO inhibitor use as this combination may prolong and intensify anti-cholinergic effects.
DIMENHYDRINATE INJECTION USP IS NOT INTENDED FOR PROLONGED USE EXCEPT ON THE ADVICE OF A PHYSICIAN.
Dimenhydrinate may impair the ability to perform hazardous activities requiring mental alertness or physical coordination such as operating machinery or driving a car. Patients receiving dimenhydrinate should be cautioned against operating automobiles or dangerous machinery because of the drowsiness associated with the drug. If drowsiness is excessive, dosage should be reduced.
The concomitant use of alcohol or other central nervous system depressants may have an additive effect and should be avoided.
Abuse/Dependence/Tolerance
Dimenhydrinate has substance abuse potential due to its hallucinogenic and euphoric effects. At higher doses, confusion, hallucinations, temporary amnesia and paranoia may occur. Chronic abuse of antihistamines can lead to drug interaction accidents, overdose, and in extreme cases to death (see OVERDOSAGE). Tolerance and psychological dependency may develop, which may lead to overdose and in some cases, even death (see OVERDOSAGE). Withdrawal symptoms may include lethargy, agitation, hostility, clumsiness, nausea, vomiting, hallucinations, confusion and aggression.
Carcinogenesis and Mutagenesis
Mutagenicity screening tests performed with dimenhydrinate, diphenhydramine, and 8-chlorotheophylline produced positive results in the bacterial systems and negative results in the mammalian systems. There are no human data that indicate dimenhydrinate is a carcinogen or mutagen or that it impairs fertility.
Cardiovascular
Use with caution in patients with cardiac arrhythmias or cardiovascular disease (including hypertension and ischemic heart disease).
Ear/Nose/Throat
Dimenhydrinate may mask the presence of underlying organic abnormalities or the toxic effects of certain antibiotics and other drugs, particularly those drugs causing ototoxicity.
Endocrine and Metabolism
Use with caution in patients who are poor CYP2D6 metabolizers and in patients with thyroid dysfunction.
Gastrointestinal
Use with caution in patients with pyloroduodenal obstruction (including stenotic peptic ulcer).
Genitourinary
Dimenhydrinate Injection USP is contraindicated in patients with prostatic hyperplasia (see CONTRAINDICATIONS). Use with caution in patients with other genitourinary obstruction.
Hematologic
Rarely, prolonged therapy with antihistaminic drugs can produce blood dyscrasia. Use with caution in patients with porphyria.
Hepatic/Biliary/Pancreatic
Use with caution in patients with hepatic impairment.
Neurologic
Dimenhydrinate should be used with caution in patients with seizure disorders.
Ophthalmologic
Dimenhydrinate is contraindicated in patients with increased intraocular pressure or narrow angle glaucoma (see CONTRAINDICATIONS).
Psychiatric
Dimenhydrinate may cause euphoria, hallucinations, confusion and paranoia at higher doses (see WARNINGS AND PRECAUTIONS; Abuse/Dependence/Tolerance)
Respiratory
Dimenhydrinate Injection USP is contraindicated in patients with chronic lung disease such as chronic obstructive pulmonary disease (see CONTRAINDICATIONS). Use with caution in patients with a history of asthma or lower respiratory tract symptoms.
Skin
In rare cases, serious skin reactions such as Stevens-Johnson syndrome, toxic epidermal necrolysis, and erythema multiform have been associated with the use of dimenhydrinate. Because the rate of these reactions is low, they have usually been noted during post-marketing surveillance in patients taking other medications also associated with the potential development of these serious skin reactions. Thus, causality is NOT clear. These reactions are potentially life threatening but may be reversible if the causative agent is discontinued and appropriate treatment instituted. Patients should be advised that if they experience a skin rash they should discontinue dimenhydrinate and contact their physician for assessment and advice, including which additional therapies to discontinue.
Special Populations
Pregnant Women: The use of dimenhydrinate by women who are pregnant or may become pregnant requires that the potential benefits be weighed against the potential hazards. There are no adequate and well-controlled studies with dimenhydrinate in pregnant women. Reproduction studies in rats and rabbits using dimenhydrinate doses up to 20 and 25 times the human dose (mg/kg), respectively, have not revealed evidence of harm to the fetus or impaired fertility.
Nursing Mothers: Small amounts of dimenhydrinate are excreted in breast milk. Because of the potential for adverse reactions in nursing infants from dimenhydrinate, a decision should be made whether to discontinue nursing or to discontinue the drug, taking into account the importance of the drug to the mother.
Labour and Delivery: The safety of dimenhydrinate injection given during labour and delivery has not been established. Reports have indicated dimenhydrinate may have oxytocic effect. Caution is advised when this effect is unwanted or in situations where it may prove detrimental.
Geriatrics: Older adults may be more sensitive to the side effects of this drug, especially drowsiness, confusion, constipation, or trouble urinating. Drowsiness and confusion can increase the risk of falling. Dimenhydrinate may be inappropriate in older adults depending on comorbidities (e.g. dementia, delirium, etc.) due to its potent anticholinergic effects.
Pediatrics (< 12 years of age): For infants and children especially, antihistamines in overdosage
may cause hallucinations, convulsions, or death (see CONTRAINDICATIONS). As in adults, antihistamines may diminish mental alertness in pediatric patients. Antihistamines may also produce excitation in younger children, therefore caution is advised in patients under 6 years of age (see INDICATIONS, Pediatrics (under 2 years of age) and CONTRAINDICATIONS).
Dimenhydrinate Injection USP is not recommended for children under 2 years of age. Discontinue use and contact the physician if symptoms of paradoxical excitation (restlessness, nervousness, hallucinations, delirium, or seizures), especially in small children, occur.
ADVERSE REACTIONS
Drowsiness and dizziness are reported most frequently, particularly on high dosage. Pain may occur at the site of IM injection. Since dimenhydrinate contains 50% diphenhydramine, the possibility of diphenhydramine side effects must also be considered.
The following adverse reactions have also been reported:
Blood and lymphatic system disorders: anemia, thrombocytopenia, agranulocytosis, leukopenia, pancytopenia.
Body as a whole - general disorders: lassitude, fatigue, drug withdrawal syndrome, injection site inflammation.
Cardiac disorders: tachycardia, palpitations, hypotension, arrhythmia.
Ear and labyrinth disorders: tinnitus, labyrinthitis, vertigo.
Eye disorders: mydriasis, vision blurred, diplopia.
Gastrointestinal disorders: epigastric distress, nausea, dry mouth, constipation, diarrhea, vomiting.
General disorders and administration site conditions: oedema.
Immune system disorders: hypersensitivity, anaphylactic reaction.
Metabolism and nutrition disorders: anorexia, decreased appetite.
Nervous system disorders: dizziness, headache, impaired coordination, somnolence, tremor, paraesthesia, ataxia, athetosis, convulsions, seizures, memory impairment, loss of consciousness.
Psychiatric disorders: depression, insomnia, hallucination, anxiety, confusional state, excitation, euphoric mood, nightmares, delirium, irritability, nervousness, restlessness, agitation.
Respiratory, thoracic, and mediastinal disorders: thickening of bronchial secretions,
respiratory depression, dyspnoea.
Renal and urinary disorders: dysuria, urinary retention.
Skin and subcutaneous tissue disorders: angioedema, hyperhidrosis, rash, rash erythematous, rash maculopapular, pruritus, urticaria, fixed drug eruption, Stevens-Johnson syndrome, toxic epidermal necrolysis, erythema multiform, photosensitivity.
Vascular disorders: hypotension, hypertension, flushing.
DRUG INTERACTIONS
Drug-Drug Interactions
CNS Depressants: Dimenhydrinate may enhance the effects of alcohol, barbiturates, tranquilizers, sedatives, or hypnotics. Caution must therefore be used to avoid overdose.
Drugs with Anticholinergic Effects: Because dimenhydrinate also has anticholinergic activity, it may potentiate the effects of other drugs with anticholinergic activity including tricyclic antidepressants, MAO inhibitors, and antihistamines. Solid potassium dose forms should be avoided as anticholinergics may slow gastrointestinal transit resulting in local exposure to high potassium concentrations.
Ototoxic Drugs: When given concurrently with aminoglycoside antibiotics or other ototoxic drugs, dimenhydrinate may mask the early symptoms of ototoxicity (see WARNINGS AND PRECAUTIONS).
Incompatibility: the incompatible substance with injectable preparations of dimenhydrinate include: phenothiazine derivatives, aminophylline, ammonium chloride, sodium amobarbital, diphenylhydantoin, sodium heparin, hydrocortisone sodium succinate, pentobarbital, phenobarbital, thiopental and certain types of antibiotics (tetracycline HCl).
Drug-Laboratory Interactions
As for other antihistamines, dimenhydrinate may inhibit the cutaneous histamine response in skin tests using allergen extracts, thus producing false- negative results. It is recommended that dimenhydrinate be discontinued at least 72 hours before testing.
DOSAGE AND ADMINISTRATION
Dosing Considerations
This preparation is designed for intramuscular (IM) use only and must not be used intravenously (IV) unless it has been diluted (see DOSAGE AND ADMINISTRATION, Intravenous Dilution Instructions below). Always inspect the solution visually for particulate
matter and discolouration prior to administration. Not to be injected intra-arterially. Substances which are physically incompatible with injectable solutions of dimenhydrinate include: phenothiazine derivatives, aminophylline, ammonium chloride, sodium amobarbital, diphenylhydantoin, heparin, hydrocortisone sodium succinate, pentobarbital, phenobarbital, thiopental and certain antibiotics.
Recommended Dose and Dosage Adjustment
Adults:
Intramuscular (IM) administration: 0.5 - 1 mL (25 - 50 mg) every 4 to 6 hours. 2 mL (100 mg) may be given every 4 – 6 hours when drowsiness is not objectionable or is even desirable. Dosage should not exceed 400 mg/day.
Intravenous (IV) administration: the usual dose is 1 mL (50 mg) diluted in 9 mL of 0.9% sodium chloride solution and injected over 2 minutes. Doses of 25 – 100 mg may be diluted in a 1:10 ratio and given every 4 – 6 hours. Diluted solutions can be stored for 24 hours at room temperature. Dosage should not exceed 400 mg/day.
Children:
Intramuscular (IM) administration:
0-2 Years of age: dimenhydrinate should not be used in children under 2 (see CONTRAINDICATIONS).
2-5 Years of age: 0.25 – 0.5 mL (12.5 - 25 mg) every 6 – 8 hours. Dosage should not exceed 75 mg/day.
6-11 Years of age: 0.5 – 1 mL (25 - 50 mg) every 6 – 8 hours. Dosage should not exceed 150 mg/day.
12-17 Years of age: 0.5 – 2 mL (25 - 100 mg) every 4 – 6 hours. Dosage should not exceed 300 mg/day (see adult administration information above).
Intravenous (IV) administration:
The same doses as indicated above diluted in a 1:10 ratio and injected over 2 minutes (see DOSAGE AND ADMINISTRATION, Intravenous Dilution Instructions).
Intravenous Dilution Instructions
For IV administration, each 1 mL of product must be diluted in 9 mL of 0.9% sodium chloride solution and injected over 2 minutes (dilution ratio 1:10). Diluted solutions can be stored up to 24 hours at room temperature. Dimenhydrinate is never to be injected intra-arterially. Always inspect the solution visually for particulate matter and discolouration prior to administration. Discard any unused portions.
OVERDOSAGE
Symptoms: Accidental antihistamine overdose occurs frequently in infants and children. Symptoms of dimenhydrinate toxicity in children may resemble atropine overdosage and include dilated pupils, flushed face, excitation, hallucinations, confusion, ataxia, intermittent clonic convulsions, coma, cardiorespiratory collapse, and death. Symptoms may be delayed up to 2
hours after ingestion; death may occur within 18 hours.
In adults, 500 mg or more of dimenhydrinate may cause extreme difficulty in speech and swallowing, and produces a psychosis indistinguishable from that of atropine poisoning. CNS excitation may be preceded by sedation, leading to a cycle of CNS excitation, seizures, and postictal depression.
Treatment: Treatment of dimenhydrinate toxicity is symptomatic and supportive. Emetics are usually ineffective, but in the absence of seizures, early gastric lavage (with an endotracheal tube with cuff inflate in place to prevent aspiration of gastric contents) may be beneficial. Patients should be kept quiet, to minimize CNS stimulation; seizures may be treated with diazepam in adults and phenobarbital in children (additional methods may include IV sodium bicarbonate, or IV physostigmine salicylate in children). Mechanical respiratory assistance may be required.
Positive and negative mode of ion mobility spectrometry (IMS) and ion mobility spectrometry/mass spectrometry (IMS/MS) have shown efficacy for the preliminary screening of emergency patients suspected of dimenhydrinate and other drug overdose.
For management of suspected drug overdose, contact your regional Poison Control Centre.
ACTION AND CLINICAL PHARMACOLOGY
Mechanism of Action
Dimenhydrinate is a theoclate salt of the ethanolamine derivative diphenhydramine. The content ratio varies from 53% - 55.5% for diphenhydramine, and 44% - 47% for 8- chlorotheophylline.
The mechanism by which dimenhydrinate exerts its antiemetic, anti-motion sickness, and antivertigo effects is not precisely known, but may possibly be related to its central anticholinergic action. Other actions may involve an effect on the medullary chemoreceptor trigger zone or dose-related inhibition of vestibular stimulation (i.e., first acting on the otolith system and in larger doses on the semicircular canals).
Pharmacokinetics
Dimenhydrinate is well absorbed after oral administration. Antiemetic effects occur almost immediately after IV administration, and within 20-30 minutes after IM administration and 15-30 minutes after oral administration. In a study of 9 healthy volunteers given a single dose of each dosage form (separated by a washout period), Tmax and Cmax are given in the following table.
| Product | Tmax (h) | Cmax (ng/mL serum) |
| Dimenhydrinate film-coated tablets 50 mg | 2.7 | 72.6 |
| Dimenhydrinate long action capsules 75 mg | 4.0 | 68.4 |
| Dimenhydrinate suppositories 100 mg | 5.3 | 112.2 |
Serum concentrations (ng/mL) 1 and 2 hours after administration of a 50 mg dimenhydrinate tablet were: 3.65 and 3.15. While not directly applicable to dimenhydrinate, it is suggested that when plasma concentration of diphenhydramine exceeds 70 ng/mL, sleep may occur.
Dimenhydrinate, like diphenhydramine, is widely distributed into body tissues, and crosses the placenta. Small amounts of dimenhydrinate are distributed into milk. After oral administration of 4x50 mg dimenhydrinate tablets, a distribution volume of 3-4 L/kg, and protein binding of 70- 85% for dimenhydrinate and 98-99% for diphenhydramine were reported. The duration of effect and therapeutic plasma level were respectively 4-6 hours and 0.1mcg/mL. The plasma elimination half-life was 5-8 hours.
Dimenhydrinate is metabolized by the liver, and excreted in urine. There are three known metabolites: diphenyl-methoxy-ethylamine, diphenyl-methoxy-acetic acid, and diphenyl- methoxy-N-methylamine.
DOSAGE FORMS, COMPOSITION AND PACKAGING
Dimenhydrinate Injection USP, 1 mL single use ampoules:
Each mL of sterile solution contains dimenhydrinate USP 50 mg in a mixture of propylene glycol (50%) and water for injection. Also contains hydrochloric acid to adjust pH. Available in 1 mL ampoules packaged in boxes of 10.
Dimenhydrinate Injection USP, 5 mL multidose vials:
Each mL of sterile solution contains dimenhydrinate USP 50 mg in a mixture of propylene glycol (50%), and water for injection. Also contains hydrochloric acid to adjust pH, and the preservatives, methylparaben 1 mg/mL (as sodium methylparaben) and propylparaben 0.1 mg/mL (as sodium propylparaben). Available in 5 mL multidose vials in boxes of 10.
STORAGE AND STABILITY
Dimenhydrinate Injection USP should be stored at room temperature (15 to 30°C). Protect from freezing. The 5 mL multidose vial should also be protected from light.
Keep out of reach and sight of children.
The Handbook on Injectable Drugs should be consulted prior to mixing dimenhydrinate with other drugs.
SPECIAL HANDLING INSTRUCTIONS
Do not use product if mixture (solution) shows haziness, particulate matter, discolouration, or leakage.
Dimenhydrinate Injection USP, packaged in 1 mL ampoules, is for single use only. Unused portions must be discarded.
Dimenhydrinate Injection USP, packaged in 5 mL vials, can be stored up to 28 days following first puncture.
The 5 mL vial stopper is not made with natural rubber latex.
PART II: SCIENTIFIC INFORMATION
PHARMACEUTICAL INFORMATION
Proper Name: Dimenhydrinate
Chemical Name: 8-chlorotheophyllinate of 2-[diphenylmethoxy]-n,n-dimethylethylamine
Other Names: IS = Anautinum; Dommanate, Dramamine®, Gravol®
Chemical Structure:
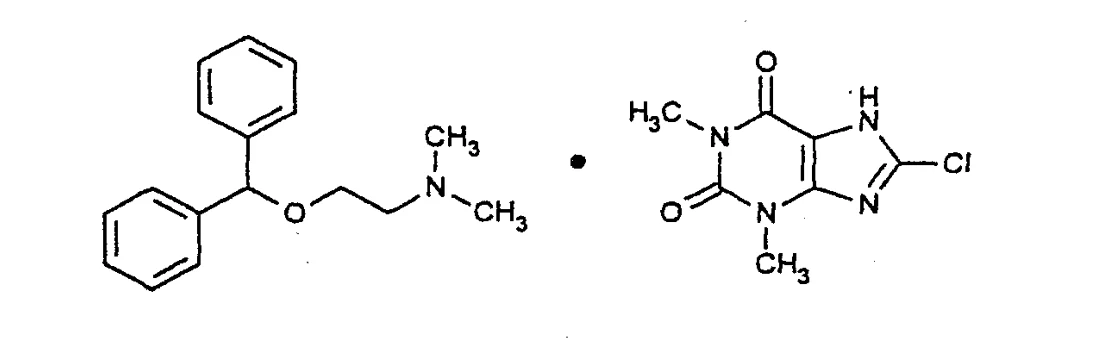
Molecular Formula: C17H21NOꞏC7H7ClN4O2
Molecular Weight: 469.97 g/mol
Physical Properties:
Physical Form: White, crystalline, odorless powder
Solubility: Slightly soluble in water; freely soluble in ethanol and in chloroform;
sparingly soluble in ether
pH Value: 6.8 – 7.3
Melting Point Range: 102°C – 107°C
TOXICOLOGY
Acute toxicity was determined by administering dimenhydrinate to mice PO and IP, and in rats PO and IV. The results are shown in the following table.
| Species | Oral | IP | IV |
| Mice | 203 mg/kg | 110 mg/kg 149 mg/kg | -- |
| Rats | 831 mg/kg 1320 mg/kg | -- | 200 mg/kg |
REFERENCES
- 1. Scavone JM, Luna BG, Harmatz JS, Moltke von L, Greenblatt DJ: Diphenhydramine kinetics following intravenous, oral and sublingual dimenhydrinate administration. Biophamaceut Drug Dispos 1990, 11: 185-189
- 2. Farrell M, Heinrichs M, Tilelli JA: Response of life threatening dimenhydrinate intoxication to sodium bicarbonate administration. Clin Toxicol 1991, 29(4): 527-535
- 3.
Le traitement des nausées et vomissement causés par la radiothérapie et la chimiothérapie.
Gravol: p. 15, 31-33. Gouvernement du Québec 1993 ISBN 2-550-28418-6
- 4. Kovac AL: Prevention and treatment of postoperative nausea and vomiting. Dimenhydrinate p.225 Drugs 2000, 59(2): 213-243.
- 5. Albert KS, Hallmark MR, Sakmar E, Weidler DJ, Wagner JG: Pharmacokinetics of diphenhydramine in man. J Pharmacokinet Biopharm 1975, 3(3): 159-170 (168-169)
- 6. Carruthers SG, Shoeman DW, Hignite ChE, Azarnoff DL: Correlation between plasma diphenhydramine level and sedative and antihistamine effects. Clin Pharmacol Ther 1978, 23(4): 375-382.
- 7.
Winn RE, McDonnell KP: Fatality secondary to massive overdose of dimenhydrinate. Ann
Emerg Med 1993, 22(9): 154/1481-157/1484 (155/1482)
- 8.
Craig DF, Mellor CS: Dimenhydrinate dependence and withdrawal. C M A J 1990, 142(9):
970-973
- 9.
Gardner DM, Kutcher St: Dimenhydrinate abuse among adolescents. Can J Psychiatr 1993,
38: 113-116.
- 10. Rowe C, Verjee Z, Koren G: Adolescent dimenhydrinate abuse: resurgence of an old problem. J Adolescents Health 1997, 21(1): 47-49
- 11. Krenzelok EP, Anderson GM, Mirick M: Massive diphenhydramine overdose resulting in death. Ann Emerg Med 1982, 11(Apr): 212-213.
- 12. Leathem AM: Safety and efficacy of antiemetics used to treat nausea and vomiting in pregnancy. (Therapy reviews antiemetics) Clin Pharm 1986, 5: 660-668
- 13. Lemay M, Samaan M, St. Michel P, Granger L, Pigeon R: Effets immédiats du dimenhydrinate sur la contraction utérine et le rythme cardiaque foetal durant le travail. C M A J 1982, 127: 606-607
- 14.
Mazzotta P, Magee LA: A risk-benefit assessment of pharmacological and
nonpharmacological treatments for nausea and vomiting of pregnancy. p.785, 787, 795-796
Drugs 2000, 59(4): 781-800
- 15. Ito Sh, Blajchman A, Stephenson M, Elipoulos Ch, Koren G: Prospective follow-up of adverse reactions in breast-fed infants exposed to maternal medication. Am J Obstet Gynecol 1993, 168(5): 1393-1399
- 16. Manning C, Scandale L, Manning EJ, Gengo FM: Central nervous system effects of meclizine and dimenhydrinate: evidence of acute tolerance to antihistamines. J Clin Pharmacol 1992, 32: 996-1002
- 17. Luria SM, Kinney JAS, McKay CL, Paulson HM, Ryan AP: Effects of aspirin and dimenhydrinate (dramamine) on visual processes. Br J Clin Pharmacol 1979, 7: 585-593
- 18. Bamforth KJ, Dagliesh K, Coughtrie MWH: Inhibition of human liver steroid sulfotransferase activities by drugs: a novel mechanism of drug toxicity. (Dimenhydrinate and diphenhydramine). Eur J Pharmacol (Environ Toxicol Pharmacol Sect) 1992, 228: 15-21
- 19.
Kivity S: Fixed drug eruption to multiple drugs: Clinical and laboratory investigation. Int J
Dermatol 1991, 30(2): 149-150
- 20.
Zavitz M, Lindsay C, McGuigan MA: Acute diphenhydramine ingestion in children. Vet
Hum Toxicol 1989, 31(4): 349 Abstr.#80
- 21. Lawrence AH, Nanji AA: Ion mobility spectrometry and ion mobility spectrometry/mass spectometric characterization of dimenhydrinate. Biomed Environ Mass Spectrom 1988, 16: 345- 347
- 22. Guay DRP, Meatherall RC, Macaulay PA, Yeung C: Activated charcoal adsorption of diphenhydramine. Int J Clin Pharmacol Ther Toxicol 1984, 22(8): 395-400
- 23.
Federal Register V, Department of Health and Human Services, FDA 21 CFR Parts 310,
336, and 369: Antiemetic drug products for over-the-counter human use: Final Rule. Effective May 2, 1988 Federal Register 1987(30.04), 52(83): 15886-15893.
- 24. Walker SE, Iazzetta J, DeAngelis C, Lau DWC: Stability and compatibility of combinations of hydromorphone and dimenhydrinate, lorazepam or prochlorperazine. Can J Hosp Pharm 1993, 46: 61-65
- 25. Oshiro Y, Balwierz PS, Piper CE: Experimental design for the C3H/10T1/2 CL8 cell transformation assay. J Appl Toxicol 1988, 8(4): 255-260
- 26.
Church & Dwight Canada Corp., Product Monograph, GRAVOLTM IM
(Dimenhydrinate), Control No. 188084, January 25, 2016.