


Product Monograph - Docetaxel Injection USP
RECENT MAJOR LABEL CHANGES
| 7 WARNINGS AND PRECAUTIONS, Reproductive Health: Female and Male Potential | 09/2024 |
|---|---|
| 7 WARNINGS AND PRECAUTIONS, 7.1.2 Breast-feeding | 06/2023 |
TABLE OF CONTENTS
Sections or subsections that are not applicable at the time of authorization are not listed.
RECENT MAJOR LABEL CHANGES ............................................................................................. 2
TABLE OF CONTENTS ............................................................................................................... 2
PART I: HEALTH PROFESSIONAL INFORMATION ....................................................................... 4
1 INDICATIONS ................................................................................................................ 4
1.1 Pediatrics ................................................................................................................. 5
1.2 Geriatrics ................................................................................................................. 5
2 CONTRAINDICATIONS .................................................................................................. 5
3 SERIOUS WARNINGS AND PRECAUTIONS BOX ............................................................. 6
4 DOSAGE AND ADMINISTRATION .................................................................................. 6
4.1 Dosing Considerations ............................................................................................. 6
4.2 Recommended Dose and Dosage Adjustment ........................................................ 7
4.3 Reconstitution ....................................................................................................... 10
4.4 Administration ....................................................................................................... 10
4.5 Missed dose ........................................................................................................... 11
5 OVERDOSAGE ............................................................................................................. 11
6 DOSAGE FORMS, STRENGTHS, COMPOSITION AND PACKAGING ................................ 11
7 WARNINGS AND PRECAUTIONS ................................................................................. 12
7.1 Special Populations................................................................................................ 17
7.1.1 Pregnant Women ............................................................................................ 17
7.1.2 Breastfeeding .................................................................................................. 17
7.1.3 Pediatrics ......................................................................................................... 17
7.1.4 Geriatrics ......................................................................................................... 17
8 ADVERSE REACTIONS ................................................................................................. 18
8.2 Clinical Trial Adverse Reactions ............................................................................. 18
8.5 Post-Market Adverse Reactions ............................................................................ 36
9 DRUG INTERACTIONS ................................................................................................. 39
9.4 Drug-Drug Interactions .......................................................................................... 39
9.5 Drug-Food Interactions .......................................................................................... 40
9.6 Drug-Herb Interactions .......................................................................................... 40
9.7 Drug-Laboratory Test Interactions ......................................................................... 40
10 CLINICAL PHARMACOLOGY ........................................................................................ 40
10.1 Mechanism of Action ....................................................................................... 40
10.2 Pharmacodynamics ......................................................................................... 40
10.3 Pharmacokinetics ............................................................................................ 41
11 STORAGE, STABILITY AND DISPOSAL .......................................................................... 42
12 SPECIAL HANDLING INSTRUCTIONS ............................................................................ 43
13 PHARMACEUTICAL INFORMATION ............................................................................. 44
14 CLINICAL TRIALS ......................................................................................................... 44
15 MICROBIOLOGY ......................................................................................................... 55
16 NON-CLINICAL TOXICOLOGY ...................................................................................... 55
17 SUPPORTING PRODUCT MONOGRAPHS ..................................................................... 64
PATIENT MEDICATION INFORMATION ................................................................................... 65
PrDOCETAXEL INJECTION USP
Docetaxel
Sterile Solution, 10 mg/mL, for Intravenous Infusion
Must be diluted directly in infusion solution
Antineoplastic Agent
PART I: HEALTH PROFESSIONAL INFORMATION
1 INDICATIONS
Breast Cancer:
Docetaxel Injection USP in combination with doxorubicin and cyclophosphamide is indicated for the adjuvant treatment of patients with operable node-positive breast cancer.
The effectiveness of docetaxel in combination with doxorubicin and cyclophosphamide (TAC) is based on improved disease-free survival and overall survival in comparison to the combination of fluorouracil, doxorubicin and cyclophosphamide (FAC). However, the positive benefit for TAC in patients with 4+ nodes was not fully demonstrated since the differences in disease-free survival (DFS) and overall survival (OS) between TAC and FAC were not statistically significant in the 4+ nodes stratum.
- Docetaxel Injection USP is indicated for the treatment of patients with locally advanced or metastatic breast cancer. Docetaxel Injection USP, in combination with doxorubicin as first line therapy, should be reserved for patients with potentially life-threatening disease (such as visceral or lung metastatic disease).
- Docetaxel Injection USP in combination with Xeloda® (capecitabine) is indicated for the treatment of patients with advanced or metastatic breast cancer after failure of prior anthracycline containing chemotherapy.
Non-Small Cell Lung Cancer:
- Docetaxel Injection USP is indicated for the treatment of patients with locally advanced or metastatic non-small cell lung cancer in monotherapy or in combination with platinum derivatives.
Ovarian Cancer:
- Docetaxel Injection USP is indicated for the treatment of metastatic carcinoma of the ovary after failure of first-line or subsequent chemotherapy.
Prostate Cancer:
- Docetaxel Injection USP in combination with prednisone or prednisolone is indicated for the treatment of patients with androgen-independent (hormone-refractory) metastatic prostate cancer.
Squamous Cell Carcinoma of the Head and Neck:
- Docetaxel Injection USP is indicated as monotherapy in the treatment of patients with recurrent and/or metastatic squamous cell carcinoma of the head and neck after failure of a previous chemotherapy regimen.
Docetaxel Injection USP should be administered under the supervision of a physician experienced in the use of antineoplastic agents.
1.1 Pediatrics
Pediatrics (<18 years of age): The safety and effectiveness of docetaxel in children have not been established (see 7.1.3 Pediatrics).
1.2 Geriatrics
Geriatrics: Evidence from clinical studies and experience suggests that use in the geriatric population is associated with differences in safety or effectiveness (see 7.1.4 Geriatrics).
2 CONTRAINDICATIONS
Docetaxel Injection USP is contraindicated in:
- patients who have a history of hypersensitivity reactions to docetaxel or any of its excipients, or to other drugs formulated with polysorbate 80 or with polyethylene glycol 300;
- pregnant women, (see 7.1.1, Pregnant Women)
- women who are breast-feeding, (see7.1.2 Breast-feeding) and
- patients with severe liver impairment.
- Docetaxel Injection USP should not be used in patients with baseline neutrophil counts of <1,500 cells/mm3.
Contraindications for other drugs also apply when combined with Docetaxel Injection USP:
- Contraindications for Xeloda® (capecitabine) also apply to the capecitabine plus Docetaxel Injection USP combination (Please refer to Xeloda® Product Monograph).
- Contraindications to prednisone also apply to the combination with Docetaxel Injection USP (Please refer to Product Monograph for prednisone).
- Contraindications to doxorubicin and cyclophosphamide also apply to their combination with Docetaxel Injection USP (Please refer to Product Monographs for doxorubicin and cyclophosphamide).
3 SERIOUS WARNINGS AND PRECAUTIONS BOX
Serious Warnings and Precautions
|
|---|
4 DOSAGE AND ADMINISTRATION
4.1 Dosing Considerations
Premedication Regimen (see below for prostate cancer): In order to reduce the incidence and severity of fluid retention, all patients should be pretreated with oral corticosteroids. The recommended premedication should consist only of oral corticosteroids, such as dexamethasone 16 mg per day (e.g. 8 mg BID), for 3 days starting one day prior to each Docetaxel Injection USP administration. Antihistamines have not been shown to be useful in controlling fluid retention.
Premedication Regimen for Prostate Cancer: For prostate cancer, given the concurrent use of prednisone or prednisolone, the recommended premedication regimen is oral dexamethasone 8 mg at 12 hours, 3 hours and 1 hour before the Docetaxel Injection USP infusion.
Prophylactic Use of Antibiotics: In order to reduce the incidence of febrile neutropenia and infections, the prophylactic use of antibiotics is recommended to patients treated for head and neck cancer. The treatment should consist of oral fluoroquinolone antibiotics, or equivalent oral or intravenous antibiotics, for 10 days starting on day 5 of each cycle of Docetaxel Injection USP administration.
Prophylactic Use of G-CSF: Prophylactic G-CSF may be used to mitigate the risk of hematological toxicities. See 4.2 Recommended Dose and Dosage Adjustment. In addition to G-CSF, the prophylactic use of antibiotics may provide additional benefit.
4.2 Recommended Dose and Dosage Adjustment
Metastatic Breast Cancer, Non-Small Cell Lung Cancer, Ovarian Cancer, and Squamous Cell Carcinoma of the Head and Neck: The recommended dosage of Docetaxel Injection USP is 100 mg/m2 administered as a one-hour infusion every 3 weeks. When used in combination, Docetaxel Injection USP is administered at the recommended dosage of 75 mg/m2.
Prostate Cancer: The recommended dosage of Docetaxel Injection USP is 75 mg/m2 administered as a one-hour infusion every 3 weeks. Concomitant treatment with prednisone or prednisolone 5 mg orally twice daily is administered continuously.
Adjuvant Treatment of Operable Node-Positive Breast Cancer: The Docetaxel Injection USP dose is 75 mg/m2 administered 1 hour after doxorubicin 50 mg/m2 and cyclophosphamide 500 mg/m2 every 3 weeks for 6 courses.
Geriatrics: Based on the population pharmacokinetics, there are no special instructions for the use in the elderly (see 7 WARNINGS AND PRECAUTIONS).
Dosing Adjustment
Patients with Neutropenia, Cutaneous Reactions or Peripheral Neuropathy: Careful monitoring of neutrophil counts is an essential part of Docetaxel Injection USP therapy. Docetaxel Injection USP should not be administered until the neutrophil count is at least 1,500 cells/ mm3. Patients who experience febrile neutropenia, severe neutropenia (neutrophil <500 cells/mm3 for more than one week), severe or cumulative cutaneous reaction, or severe neurosensory signs and/or symptoms during Docetaxel Injection USP therapy should have the dosage of Docetaxel Injection USP reduced from 100 mg/m2 to 75 mg/m2. When Docetaxel Injection USP is given in combination, the dose of Docetaxel Injection USP should be reduced from 75 mg/m2 to 60 mg/m2. If the patient continues to experience these reactions at 60 mg/m2, the treatment should be discontinued. Alternatively, prophylactic G-CSF may be used in patients with either prior febrile neutropenia or severe infection in order to maintain dose intensity (see 7 WARNINGS AND PRECAUTIONS).
Patients who receive adjuvant therapy for breast cancer and who experience febrile neutropenia should receive G-CSF in all subsequent cycles. Patients who continue to experience this reaction should remain on G-CSF and have their Docetaxel Injection USP dose reduced to 60 mg/m2. If G-CSF is not used, the Docetaxel Injection USP dose should be reduced from 75 to 60 mg/m2. Patients who experience grade 3 or 4 stomatitis should have their dose decreased from 75 to 60 mg/m2.
Patients with Hepatic Impairment: Docetaxel Injection USP should not be used in patients with serum bilirubin > ULN. Also, Docetaxel Injection USP should not be used in patients who have ALT and/or AST > 1.5 x ULN concomitant with alkaline phosphatase > 2.5 x ULN.
The amount of ethanol in Docetaxel Injection USP should be taken into account when given to patients with hepatic impairment (see 7 WARNINGS AND PRECAUTIONS).
Concomitant use with a potent CYP3A4 inhibitor: if systemic administration of a potent CYP3A4 inhibitor cannot be avoided, a dose reduction of Docetaxel Injection USP should be considered and close monitoring for toxicity is recommended (see 7 WARNINGS AND PRECAUTIONS, General and 9 DRUG INTERACTIONS).
Docetaxel Injection USP in Combination with Capecitabine
Table 1: Recommended Dose Modifications for Combination Therapy with Capecitabine
| Grade 2 | Grade 3 | Grade 4 | |
|---|---|---|---|
| 1st appearance | Interrupt treatment until resolved to grade 0-1 then continue at same doses with prophylaxis where possible. | Grade 3 at time Docetaxel Injection USP treatment due: interrupt treatment and delay for a maximum of two weeks until grade 0-1 then continue at 75% of original capecitabine dose and at 55 mg/m2 of Docetaxel Injection USP with prophylaxis where possible. If no recovery to grade 0-1 within two weeks delay, patient will stop Docetaxel Injection USP therapy but may restart capecitabine at 75% of original capecitabine dose when grade 0-1. Grade 3 occurring between cycles with recovery to grade 0-1 by the time the next treatment due: continue at 75% of original capecitabine dose and at 55 mg/m2 of Docetaxel Injection USP with prophylaxis where possible. | Discontinue capecitabine and Docetaxel Injection USP treatment unless treating physician considers it to be in the best interest of the patient to continue with capecitabine monotherapy at 50% of original dose. |
| 2nd appearance of same toxicity | Interrupt treatment until resolved to grade 0-1, then continue at 75% of original capecitabine dose and at 55 mg/m2 of Docetaxel Injection USP. | Discontinue Docetaxel Injection USP treatment and interrupt capecitabine treatment until resolved to grade 0-1, then continue at 50% of original capecitabine dose. | |
| 3rd appearance of same toxicity | Interrupt treatment until resolved to grade 0-1, then continue at 50% of original capecitabine dose and discontinue Docetaxel Injection USP. | Discontinue treatment. |
| Grade 2 | Grade 3 | Grade 4 | |
|---|---|---|---|
| 4th appearance of same toxicity | Discontinue treatment. |
4.3 Reconstitution
Preparation of the Infusion Solution:
- 1. If the vials are stored under refrigeration, allow the required number of Docetaxel Injection USP vials to stand at room temperature for approximately 5 minutes.
- 2. Aseptically withdraw the required amount of Docetaxel Injection USP (10 mg/mL) with a calibrated syringe and inject the required volume into a 250 mL infusion bag or bottle of either 0.9% Sodium Chloride solution or 5% Dextrose solution to produce a final concentration of 0.3 to 0.74 mg/mL. If a dose greater than 200 mg of Docetaxel Injection USP is required, use a larger volume of the infusion vehicle so that a concentration of 0.74 mg/mL Docetaxel Injection USP is not exceeded.
- 3. Thoroughly mix the infusion by manual rotation.
- 4. As with all parenteral products, Docetaxel Injection USP should be inspected visually for particulate matter or discoloration prior to administration whenever the solution and container permit. If the Docetaxel Injection USP is not clear or appears to have precipitation, the solution should be discarded.
Docetaxel Injection USP should be aseptically administered intravenously as a 1-hour infusion under ambient room temperature and lighting conditions.
Contact of the undiluted concentrate with plasticized PVC equipment or devices used to prepare solution for infusion is not recommended. In order to minimize patient exposure to plasticizer DEHP (di-2-ethylhexyl phthalate), which may be leached from PVC infusion bags or sets, Docetaxel Injection USP infusion solution should be stored in bottles (glass, polypropylene) or plastic bags (polypropylene, polyolefin) and administered through polyethylene-lined administration sets.
4.4 Administration
Precautions: Docetaxel Injection USP must be administered intravenously. It is extremely important that the intravenous needle or catheter be properly positioned before any Docetaxel Injection USP is injected. Leakage into surrounding tissue during intravenous administration of Docetaxel Injection USP may cause considerable irritation, local tissue necrosis and/or thrombophlebitis. If extravasation occurs, the injection should be discontinued immediately, and any remaining portion of the dose should be introduced into another vein.
Docetaxel Injection USP solution must be diluted directly in 0.9% Sodium chloride solution or 5% dextrose solution prior to administration (see 4.3 Reconstitution).
Injection site recall reactions (recurrence of skin reaction at a site of previous extravasation following administration of docetaxel at a different site) have been observed.
Please refer to the 12 SPECIAL HANDLING INSTRUCTIONS.
4.5 Missed dose
This medicine needs to be given on a fixed schedule. If an appointment is missed, the patient should consult with their healthcare professional team to determine the appropriate course of action.
5 OVERDOSAGE
There is no known antidote for Docetaxel Injection USP overdosage. In case of overdosage, the patient should be kept in a specialized unit where vital functions can be closely monitored and supportive treatment administered as necessary. Anticipated complications of overdosage include: bone marrow suppression, peripheral neurotoxicity, and mucositis. Patients should receive therapeutic G-CSF as soon as possible after discovery of overdose. Other appropriate symptomatic measures should be taken, as needed.
There were a few reports of overdose. One patient received 150 mg/m2 and the other received 200 mg/m2 as a one-hour infusion. Some patients experienced severe neutropenia, mild asthenia, cutaneous reactions, and mild paresthesia, and recovered without incident.
| For management of a suspected drug overdose, contact your regional poison control centre. |
|---|
6 DOSAGE FORMS, STRENGTHS, COMPOSITION AND PACKAGING
Table 2 – Dosage Forms, Strengths, Composition and Packaging
Docetaxel Injection USP is a clear colourless to pale yellow solution that must be added to infusion solution. Docetaxel Injection USP is sterile, non-pyrogenic, and is available as a single-
| Route of Administration | Dosage Form / Strength/Composition | Non-medicinal Ingredients |
| Intravenous Infusion | Solution, 10 mg/mL Docetaxel Injection USP must be diluted directly to infusion solution before use. For detailed instructions, see 4.3 Reconstitution. | Citric acid (anhydrous), ethanol anhydrous, polyethylene glycol 300, polysorbate 80 |
dose vial in a 2 mL presentation and as multidose vials in 8 mL or 16 mL presentations in clear Type I conventional glass vials with latex-free stoppers. Each vial is wrapped in a clear plastic ONCO-TAIN® sleeve. Each mL contains 10 mg docetaxel (anhydrous), 260 mg polysorbate 80, 0.23 mL (181 mg) ethanol anhydrous, 4.0 mg citric acid (anhydrous) and q.s. to 1.00 mL with polyethylene glycol 300.
7 WARNINGS AND PRECAUTIONS
Please see 3 SERIOUS WARNINGS AND PRECAUTIONS BOX
General
All patients should be premedicated with an oral corticosteroid such as dexamethasone 16 mg per day (e.g., 8 mg BID) for 3 days starting one day prior to docetaxel administration to reduce the incidence and severity of fluid retention as well as the severity of hypersensitivity reactions.
The pretreatment regimen for prostate cancer (given the concurrent use of prednisone or prednisolone) is oral dexamethasone 8 mg, 12 hours, 3 hours and 1 hour before the docetaxel infusion (see 4.1 Dosing considerations, Premedication).
Concomitant use of docetaxel and drugs that inhibit CYP3A4 may increase exposure to docetaxel and should be avoided. In patients receiving treatment with docetaxel, close monitoring for toxicity and a docetaxel dose reduction could be considered if systemic administration of a potent CYP3A4 inhibitor cannot be avoided (see 9 DRUG INTERACTIONS).
There are no clinical data with a dose adjustment in patients receiving strong CYP3A4 inhibitors. Based on extrapolation from a pharmacokinetic study with ketoconazole in 7 patients, consider a 50% docetaxel dose reduction if patients require co-administration of a strong CYP3A4 inhibitor.
The amount of ethanol in Docetaxel Injection USP may be harmful in patients suffering from alcoholism and should also be taken into account in children and in high-risk groups such as patients with liver disease or epilepsy. Consideration should be given to possible effects on the central nervous system. The amount of ethanol in Docetaxel Injection USP may impair the ability to drive or use machines (see 7 WARNINGS AND PRECAUTIONS, Neurologic).
The amount of ethanol in Docetaxel Injection USP may alter the effects of other medicinal products (see 9 DRUG INTERACTIONS).
Carcinogenesis and Mutagenesis
Second Primary Malignancies: Second primary malignancies have been reported in patients treated with docetaxel (as monotherapy and when given in combination with anticancer treatments known to be associated with second primary malignancies). Second primary malignancies (including acute myeloid leukemia, myelodysplastic syndrome, non-Hodgkin lymphoma and renal cancer) may occur several months or years after docetaxel-containing therapy.
Treatment-related acute myeloid leukemia (AML) may occur. In the adjuvant breast cancer trial (TAX316) at a median follow-up of 96 months, AML was reported in 4 of 744 patients who received docetaxel, doxorubicin and cyclophosphamide (TAC) and in 1 of 736 patients who received 5-fluorouracil, doxorubicin and cyclophosphamide (FAC). Myelodysplastic syndrome (MDS) was reported in 2 of 744 patients who received TAC and in 1 of 736 patients who received FAC.
In patients treated with docetaxel, doxorubicin and cyclophosphamide (TAC) as adjuvant therapy for breast cancer, the risk of delayed myelodysplasia or myeloid leukemia requires hematological follow-up (see 8 ADVERSE REACTIONS). All patients treated with docetaxel-containing regimens should be monitored for second primary malignancies (see 8 ADVERSE REACTIONS).
Docetaxel has been shown to be mutagenic in the in vitro chromosome aberration test in CHO-K1 cells and in the in vivo micronucleus test in the mouse.
The carcinogenic potential of docetaxel has not been studied. However, given that docetaxel is unequivocally genotoxic, it should be presumed to be a human carcinogen (see 16 NON-CLINICAL TOXICOLOGY).
Cardiovascular
Ventricular arrhythmia (including sometimes fatal ventricular tachycardia, fibrillation and extrasystole) has been reported in patients treated with docetaxel in combination regimens including, but not limited to, doxorubicin, 5-fluorouracil and/or cyclophosphamide (see 8.5 Post-Market Adverse Drug Reactions). Baseline cardiac assessment is recommended.
Endocrine and Metabolism
Tumor Lysis Syndrome: Tumor lysis syndrome, including fatal cases, has been reported in patients treated with docetaxel. Patients at risk of tumor lysis syndrome (i.e. those with renal impairment, hyperuricemia, bulky tumor) should be closely monitored in order to properly manage this syndrome. Correction of dehydration and treatment of high uric acid levels are recommended prior to initiation of treatment.
Fluid Retention
Severe fluid retention has been reported following docetaxel therapy. Therefore, patients should be premedicated with oral corticosteroids prior to each Docetaxel Injection USP administration to reduce the incidence and severity of fluid retention (see 4 DOSAGE AND ADMINISTRATION). Patients with preexisting severe fluid retention such as pleural effusion, pericardial effusion and ascites should be closely monitored from the first dose for the possible exacerbation of the effusions.
Gastrointestinal
Caution is recommended for patients with neutropenia, who are particularly at risk for developing gastrointestinal complications. Enterocolitis could develop at any time, and could lead to death as early as on the first day of onset. Patients should be closely monitored for early manifestations of serious gastrointestinal toxicity (see 7 WARNINGS AND PRECAUTIONS, Hematologic and 8.5 Post-Market Adverse Drug Reactions).
Hematologic
Neutropenia is the most frequently reported adverse event. Neutrophil nadirs occurred at a median of 7 days, but this interval may be shorter in heavily pretreated patients. Docetaxel Injection USP therapy should not be administered until the neutrophil count is over 1,500 cells/mm3. In order to monitor the occurrence of myelotoxicity, it is recommended that frequent blood cell counts be performed on all patients receiving Docetaxel Injection USP. Patients should not be retreated with subsequent cycles of Docetaxel Injection USP until neutrophils recover to a level of >1,500 cells/mm³. In cases of severe neutropenia (<500 cells/mm3) for seven days or more during a course of Docetaxel Injection USP therapy, a reduction in dose for subsequent courses of therapy or the use of appropriate systematic measures are recommended (see 4 DOSAGE AND ADMINISTRATION).
Hepatic/Biliary/Pancreatic
In patients treated with Docetaxel Injection USP who have total bilirubin greater than the upper limit of normal (ULN) or transaminase (ALT and/or AST) greater than 1.5 times the ULN concurrent with alkaline phosphatase greater than 2.5 times the ULN, there is a higher risk of developing severe adverse reactions such as toxic deaths, including sepsis and gastrointestinal hemorrhage which can be fatal, febrile neutropenia, infections, thrombocytopenia, stomatitis and asthenia. The severe or life-threatening complications have been reported in these patients at subclinical doses. Docetaxel Injection USP should not be used in patients with total serum bilirubin > ULN or in patients with ALT and/or AST > 1.5 x ULN concurrent with alkaline phosphatase > 2.5 x ULN. Liver function tests (LFTs) should be measured at baseline and before each cycle.
The amount of ethanol in Docetaxel Injection USP should be taken into account when given to patients with hepatic impairment (see 7 WARNINGS AND PRECAUTIONS, Neurologic).
Immune
Hypersensitivity Reactions: Severe hypersensitivity reactions characterized by severe hypotension, bronchospasm, generalized rash/erythema or very rarely fatal anaphylaxis have been reported in patients who received premedication. These reactions resulted in immediate discontinuation in approximately 0.4% (5 of 1260) of patients. Severe symptoms resolve after discontinuation of the infusion and administration of appropriate therapy.
Patients should be observed closely for hypersensitivity reactions especially during the first and second infusions. Hypersensitivity reactions may occur within a few minutes following the initiation of the infusion of Docetaxel Injection USP, thus facilities for the treatment of hypotension and bronchospasm should be available. Severe reactions require immediate discontinuation of Docetaxel Injection USP and aggressive therapy. Patients who have developed severe hypersensitivity reactions should not be rechallenged with Docetaxel Injection USP. If minor reactions such as flushing or localized skin reactions occur, therapy with Docetaxel Injection USP does not have to be discontinued. All patients should be premedicated with an oral corticosteroid prior to the initiation of the infusion of Docetaxel Injection USP (see 4 DOSAGE AND ADMINISTRATION).
Patients who have previously experienced a hypersensitivity reaction to paclitaxel may develop a potentially fatal hypersensitivity reaction to Docetaxel Injection USP.
Neurologic
The development of severe peripheral neurotoxicity is infrequent and requires a reduction in dose (see 4 DOSAGE AND ADMINISTRATION). If symptoms persist, treatment should be discontinued.
Alcohol content: Docetaxel concentrate for infusion contains ethanol (181 mg/ml), which is harmful for those suffering from alcoholism. Cases of alcohol intoxication have been reported with some formulations of docetaxel due to the alcohol content. Each intravenous administration of Docetaxel Injection USP (at 100 mg/m2) delivers approximately 1.81 g/m2 of alcohol. The alcohol content in a dose of docetaxel should be taken into account for patients in whom alcohol intake should be avoided or minimized, including pregnant or breastfeeding women and high-risk groups such as patients with hepatic impairment or epilepsy. Some medications, such as CNS depressants, pain relievers and sleep aids may interact with the alcohol in the docetaxel infusion and exacerbate depression or worsen the intoxicating effects (see 9 DRUG INTERACTIONS). Consideration should be given to possible effects on the central nervous system. Co-administration with medicines containing e.g. propylene glycol or ethanol may lead to accumulation of ethanol and induce adverse effects. Monitor patients for signs of alcohol intoxication during and after treatment. Patients should be advised not to drive or use machines immediately after the infusion.
Ophthalmologic
Cystoid macular edema (CME) has been reported in patients treated with docetaxel, as well as with other taxanes (see 8.5 Post-Market Adverse Drug Reactions). Patients with impaired vision during Docetaxel Injection USP treatment should undergo a prompt and complete ophthalmologic examination. In case CME is diagnosed, Docetaxel Injection USP treatment should be discontinued and if necessary appropriate treatment initiated. CME is usually reversible upon discontinuation of taxane therapy.
Renal
A dose reduction of Xeloda® (capecitabine) to 75% is recommended when used in combination with docetaxel in patients with moderate renal impairment (Please refer to Xeloda® Product Monograph).
Reproductive Health: Female and Male Potential
Contraception in males and females
Based on reproductive toxicity and genetic toxicity findings, women of childbearing potential should be advised to use effective contraception during treatment with docetaxel and for at least 2 months after the last dose.
Based on genetic toxicity findings, male patients with female partners of childbearing potential should be advised to use effective contraception during treatment with docetaxel and for at least 4 months after the last dose.
- Fertility
In non-clinical studies, non-reversible testicular changes, such as testicular atrophy, arrested maturation of the germ cells or degeneration of seminiferous tubular epithelium, were observed in animal treated with docetaxel at doses below those used in the clinic. An adverse effect on male fertility cannot be excluded. Therefore, men should be counselled to seek advice on conservation of sperm prior to treatment.
- Teratogenic Risk
Docetaxel has been shown to be both embryotoxic and fetotoxic in rabbits and rats – causing intrauterine mortality, reduced fetal weight and fetal ossification delays – and to reduce fertility in rats. These effects are consistent with maternal toxicity. As with other cytotoxic drugs, docetaxel may cause fetal harm when administered to pregnant women. Therefore, Docetaxel Injection USP must not be used during pregnancy. (see 2 CONTRAINDICATIONS and 7.1.1 Pregnant Women).
Respiratory
Acute respiratory distress syndrome, interstitial pneumonia/pneumonitis, interstitial lung disease, lung infiltration, pulmonary fibrosis, respiratory failure, and radiation recall phenomena have been reported, and have occasionally been associated with fatal outcome. Cases of radiation pneumonitis have been reported in patients receiving concomitant radiotherapy.
Skin
Localized erythema of the extremities (palm of the hands and soles of the feet) with edema, followed by desquamation has been observed. In case of severe skin toxicity during a course of Docetaxel Injection USP therapy, a reduction in dose for subsequent courses of therapy is recommended (see 4 DOSAGE AND ADMINISTRATION).
Severe Cutaneous Adverse Reactions (SCARs) such as Stevens-Johnson Syndrome (SJS), toxic epidermal necrolysis (TEN) and acute generalized exanthematous pustulosis (AGEP) have been reported in association with docetaxel treatment. Patients should be informed about the signs and symptoms of serious skin manifestations and monitored closely. In case SCARs are observed, permanent treatment discontinuation should be considered.
Driving/Operating Machinery
Since Docetaxel concentrate for infusion contains ethanol, consideration should be given to the possibility of CNS and other effects. This may include impairment of a patient’s ability to drive or use machines immediately after infusion.
7.1 Special Populations
7.1.1 Pregnant Women
Docetaxel Injection USP may cause fetal harm when administered to a pregnant woman (7 WARNINGS AND PRECAUTIONS, Teratogenic Risk). There is no information on the use of docetaxel during pregnancy. Therefore, Docetaxel Injection USP must not be used during pregnancy (see 2 CONTRAINDICATIONS). Women of childbearing age and receiving Docetaxel Injection USP should be advised to avoid becoming pregnant, and to inform the treating physician immediately should this occur. Should the patient become pregnant while receiving this drug, the patient should be apprised of the potential hazard to the fetus.
7.1.2 Breastfeeding
It is not known whether docetaxel is excreted in human milk. Because many drugs are excreted in human milk, and because of the potential for serious adverse reactions in nursing infants from docetaxel, breastfeeding must be discontinued during docetaxel therapy and for 1 week after the last dose.
7.1.3 Pediatrics
Pediatrics (<18 years of age): The safety and effectiveness of docetaxel in children have not been established.
7.1.4 Geriatrics
Those with poor performance status, or otherwise non-life-threatening indolent disease (such as relatively asymptomatic metastatic disease limited to the bone) should be considered as possible candidates for less toxic therapies prior to consideration of a docetaxel based therapy.
An analysis of safety data in patients equal or greater than 60 years of age showed an increase in the incidence of treatment-related grade 3 and 4 adverse events when treated with docetaxel in combination with Xeloda®. Treatment-related serious adverse events and early withdrawals from treatment due to adverse events were lower in patients of less than 60 years of age.
Of the 332 patients treated with docetaxel every three weeks plus prednisone in the prostate cancer study (TAX327), 208 patients were 65 years of age or greater and 67 patients were older than 75 years. In patients treated with docetaxel every three weeks, the following treatment emergent adverse events (TEAEs) occurred at rates ≥ 10% higher in patients 65 years of age or greater compared to younger patients: anemia (71% vs. 59%), infection (37% vs. 24%), nail changes (34% vs. 23%), anorexia (21% vs. 10%), weight loss (15% vs. 5%) respectively.
8 ADVERSE REACTIONS
8.2 Clinical Trial Adverse Reactions
Clinical trials are conducted under very specific conditions. The adverse reaction rates observed in the clinical trials; therefore, may not reflect the rates observed in practice and should not be compared to the rates in the clinical trials of another drug. Adverse reaction information from clinical trials may be useful in identifying and approximating rates of adverse drug reactions in real-world use.
DOCETAXEL INJECTION USP AS A SINGLE AGENT
Two thousand one hundred and six (2106) patients received an initial dose of 100 mg/m2 of docetaxel as a single agent over a one-hour infusion independently of the pre-medication for the treatment of various tumor types. The patients were enrolled in 40 clinical trials conducted in North America and Europe (breast carcinoma, n= 991; non-small cell lung cancer, n= 634). The following table lists adverse reaction data from 2045 patients with normal LFTs at baseline and 61 patients with elevated LFTs at baseline.
Additionally, 96 patients enrolled in 3 clinical trials received an initial dose of 100 mg/m2 of docetaxel as a single agent over a one-hour infusion every 3 weeks for the treatment of recurrent and/or metastatic squamous cell carcinoma of the head and neck.
These reactions were considered possibly or probably related to docetaxel. The safety profile is generally similar in all patients whether they were treated for breast carcinoma or for other tumor types (e.g. ovarian cancer).
Clinical Trial Adverse Drug Reactions
Table 3: Summary of Adverse Events in Patients receiving Docetaxel as a Single Agent
| Docetaxel as a Single Agent (100 mg/m2) | ||||||||||
|---|---|---|---|---|---|---|---|---|---|---|
| Various Tumor Types Including: Breast Carcinoma, Non-small Cell Lung Cancer and Ovarian Cancer | Squamous Cell Carcinoma of the Head and Neck | |||||||||
Normal LFTs* at Baseline N=2045 (%) | Elevated LFTs at Baseline N=61 (%) | Normal LFTs* at Baseline N=96 (%) | ||||||||
| Alopecia | 75.8 | 62.3 | 85.4 | |||||||
Arthralgia
| 9.2 0.6 | 6.6 0 | 5.5 [n=54] 0 [n=54] | |||||||
Asthenia
| 61.8 12.8 | 52.5 24.6 | 63.5 20.8 | |||||||
Cutaneous
| 47.6 4.8 | 57.4 9.8 | 39.6 3.1 | |||||||
Fever In Absence Of Infection
| 32.1 2.1 | 41.0 8.2 | 29.2 [n=65] 1.5 [n=65] | |||||||
Fluid Retention
| 47.0 6.9 | 54.1 9.8 | 28.1 4.2 | |||||||
Gastrointestinal Nausea (All)
Diarrhea (All)
Vomiting (All)
| 38.9 3.9 39.0 4.7 22.3 2.7 | 37.7 4.9 32.8 4.9 23.0 4.9 | 19.8** - 15.6 - 15.6** - | |||||||
Hypersensitivity Reactions
| 21.0 4.2 | 19.7 9.8 | 16.7 3.1 | |||||||
Infusion Site Reaction
| 4.4 | 3.3 | - | |||||||
Myalgia
| 18.9 1.5 | 16.4 1.6 | 16.7 [n=66] 0 [n=66] | |||||||
| Docetaxel as a Single Agent (100 mg/m2) | |||||||||
|---|---|---|---|---|---|---|---|---|---|
| Various Tumor Types Including: Breast Carcinoma, Non-small Cell Lung Cancer and Ovarian Cancer | Squamous Cell Carcinoma of the Head and Neck | ||||||||
Normal LFTs* at Baseline N=2045 (%) | Elevated LFTs at Baseline N=61 (%) | Normal LFTs* at Baseline N=96 (%) | |||||||
Nail Changes
| 30.6 2.5 | 23.0 4.9 | 28.1 - | ||||||
Neuromotor
| 13.8 3.6 | 6.6 1.6 | 7.1 [n=41] 1.0 [n=41] | ||||||
Neurosensory
| 49.3 4.3 | 34.4 0 | 37.9 [n=66] 3.1 [n=66]# | ||||||
| Non-Septic Death | 0.3 | 6.6 | NR | ||||||
| Septic Death | 1.4 | 3.3 | 1.0 | ||||||
Stomatitis
| 41.7 5.5 | 49.2 13.1 | 29.2 6.3 | ||||||
* Normal liver function tests (LFTs): transaminase ≤ 1.5 times upper limit of normal or alkaline phosphatase ≤ 2.5 times upper limit of normal or isolated elevations of transaminase or alkaline phosphatase up to 5 times upper limit of normal. # Includes 2 patients who were counted as having peripheral neuropathy. ** Includes one patient with combined nausea/vomiting. NR = Not reported | |||||||||
Table 4: Summary of Haematologic Adverse Events in Patients Receiving Docetaxel as a Single Agent
| Docetaxel as a Single Agent (100 mg/m2) | ||||||||
|---|---|---|---|---|---|---|---|---|
| Various Tumor Types Including: Breast Carcinoma, Non-small Cell Lung Cancer and Ovarian Cancer | Squamous Cell Carcinoma of the Head and Neck | |||||||
Normal LFTs* at Baseline N=2045 (%) | Elevated LFTs at Baseline N-61 (%) | Normal LFTs* at Baseline N=96 (%) | ||||||
Anemia < 11 g/dL
| 90.4 8.8 | 91.8 31.2 | 90.8 [n=65] 0 [n=65] | |||||
| Febrile Neutropenia | 11.0 | 24.5 | 24.0** | |||||
| Docetaxel as a Single Agent (100 mg/m2) | ||||||||
|---|---|---|---|---|---|---|---|---|
| Various Tumor Types Including: Breast Carcinoma, Non-small Cell Lung Cancer and Ovarian Cancer | Squamous Cell Carcinoma of the Head and Neck | |||||||
Normal LFTs* at Baseline N=2045 (%) | Elevated LFTs at Baseline N-61 (%) | Normal LFTs* at Baseline N=96 (%) | ||||||
Infection
| 21.6 6.1 | 32.8 16.4 | - - | |||||
Leukopenia < 4,000 cells/mm3
| 95.6 31.6 | 98.3 46.6 | 86.3 [n=95] 20.0 [n=95] | |||||
Neutropenia < 2,000 cells/mm3
| 95.5 75.4 | 96.4 87.5 | 95.4 [n=65] 69.2 [n=65] | |||||
Thrombocytopenia < 100,000 cells/mm3
| 8.0 0.5 | 24.6 4.9 | 3.1 [n=65] - | |||||
* Normal liver function tests (LFTs): transaminase ≤ 1.5 times upper limit of normal or alkaline phosphatase ≤ 2.5 times upper limit of normal or isolated elevations of transaminase or alkaline phosphatase up to 5 times upper limit of normal. ** Includes 16 patients who were counted as having febrile leukopenia requiring hospitalization (defined as WBC count ≤ 1000/mcL associated with fever ≥38°C requiring hospitalization). | ||||||||
Cardiovascular: Hypotension occurred in 3% of the patients and required therapy in 0.5% of the patients treated with docetaxel as a single agent for various tumor types. Dysrhythmia occurred in 2% of the patients and was severe in 0.4% of the patients. Clinically meaningful events occurred in less than 2% of patients. These events included: heart failure (0.3%), tachycardia (1.4%), and hypertension (1.6%).
Cutaneous: Cutaneous reactions have been observed in 48% of the patients treated with docetaxel as a single agent for various tumor types. These reactions were characterized by a rash, including localized eruptions mainly on feet and hands (including severe hand and foot syndrome), but also on arms, face or thorax. They were frequently associated with pruritus. Eruptions generally occurred within one week following the docetaxel infusion, resolved before the next infusion, and were not disabling.
Severe symptoms such as eruptions followed by desquamation occurred less frequently (5%). These reactions rarely led to interruption or discontinuation of docetaxel treatment.
Severe nail disorders occurred in ≤ 3% of the patients treated with docetaxel as a single agent. These reactions were characterized by hypo- or hyperpigmentation, and infrequently onycholysis and pain.
Alopecia was observed in 76% of patients treated with docetaxel as a single agent for various tumor types (0.5% severe), and in 85% of patients treated for recurrent and/or metastatic squamous cell carcinoma of the head and neck (SCCHN).
Fluid Retention: Fluid retention which includes edema, and less frequently, pleural effusion, ascites, pericardial effusion, and weight gain, usually begins at the lower extremities and may become generalized with a weight gain of 3 kg or more. Fluid retention is cumulative in incidence and severity (see 7 WARNINGS AND PRECAUTIONS, General).
The incidence of fluid retention in patients treated with docetaxel as a single agent and without premedication was 81.6%; of these 22.4% were severe. In patients treated for various tumor types and premedicated for 3 days with oral corticosteroids, the incidence of fluid retention was 64.1% (6.5% were severe). Fluid retention was reported in 24% for patients treated for recurrent and/or metastatic SCCHN. Below is a table describing the effect on fluid retention with corticosteroid premedication (see 4 DOSAGE AND ADMINISTRATION section for premedication regimen).
Table 5: Effects of Corticosteroid Premedication on the Incidence of Fluid Retention
| Incidence | Severe | |||
|---|---|---|---|---|
Without Premedication 3-day Premedication* | 81.6% 64.1% | 22.4% 6.5% | ||
| *Fluid retention adverse reactions have been obtained from 92 patients treated with Docetaxel as single agent, 100 mg/m2, from a retrospective analysis on the 3-day premedication regimen. | ||||
In patients treated by docetaxel as single agent, at 100 mg/m2, the median cumulative dose to treatment discontinuation was more than 1,000 mg/m2 and the median time to fluid retention reversibility was 16.4 weeks (range: 0 to 42 weeks). The onset of moderate and severe retention is delayed (median cumulative dose: 818.9 mg/m2) in patients with premedication compared with patients without premedication (median cumulative dose: 489.7 mg/m2); however, it has been reported in some patients during early courses of therapy. Fluid retention has not been accompanied by oliguria or hypotension, and was slowly reversible after docetaxel treatment was stopped.
Gastrointestinal: Nausea (39%), diarrhea (39%), and vomiting (22%), were observed in patients treated with docetaxel as a single agent for various tumor types. They were less frequent in patients treated for recurrent and/or metastatic SCCHN (20%, 16% and 16% respectively). These reactions were generally mild to moderate. Severe gastrointestinal reactions generally occurred in less than 5% of the cases reported. Stomatitis was reported by 42% and by 29% of patients treated for various tumor types and for recurrent and/or metastatic SCCHN, respectively. Other gastrointestinal events included anorexia, taste perversion, constipation, abdominal pain, gastrointestinal bleeding and esophagitis.
Hematologic: Bone marrow suppression and other hematologic adverse reactions to docetaxel include neutropenia, febrile neutropenia, thrombocytopenia and anemia, have been reported.
Neutropenia was the most frequent adverse reaction associated with docetaxel, and it was reversible and not cumulative. The median time to nadir was 7 days; while the median duration of severe neutropenia (< 500 cells/mm3) was 7 days. Severe neutropenia occurred in 75% of the patients treated with docetaxel as a single agent for various tumor types and 69% in patients with recurrent and/or metastatic SCCHN.
When treated with docetaxel as a single agent, fever was associated with neutropenia (<500 cells/mm3) in 11% of the patients with normal liver function (3% of the cycles) treated for various tumor types and in 24% of patients treated for recurrent and/or metastatic SCCHN. The incidence of severe infections associated with neutrophil counts <500 cells/mm3 was 6% of the patients (1.3% of the cycles). Infectious episodes, which included sepsis and pneumonia, occurred in 22% of the patients (6% of the cycles) and were fatal in approximately 1.7% of patients treated with docetaxel as a single agent for various tumor types. Septic death was reported less frequently (1%) in patients treated for recurrent and/or metastatic SCCHN.
Thrombocytopenia (< 100,000 cells/mm3) has been reported in 8% of the patients treated with docetaxel as a single agent for various tumor types and 3.1% of patients treated for recurrent and/or metastatic SCCHN. Bleeding episodes were reported in 1% of the patients; this was associated with severe thrombocytopenia (<50,000 cells/mm3) in only two patients. A fatal gastrointestinal hemorrhage due to thrombocytopenia was reported in one patient.
Anemia (< 11 g/dL) was observed in 90% of the patients treated with docetaxel as a single agent and was severe (< 8 g/dL) in 9% of the cases. It was not reported in patients treated for recurrent and/or metastatic SCCHN.
Hepatic: Increases in alanine transferase (ALT), aspartate transferase (AST), bilirubin, and alkaline phosphatase which were greater than 2.5 times the upper limit of normal were observed in less than 5% of patients treated with docetaxel as a single agent for various tumor types.
Hypersensitivity Reactions: Hypersensitivity reactions occurred in 21% of the patients treated with docetaxel as a single agent for various tumor types and in 17% of patients treated for recurrent and/or metastatic SCCHN. The reactions occurred generally within a few minutes following the start of the infusion of docetaxel and were usually mild to moderate. The most frequent minor manifestations were flushing, rash with or without pruritus, chest tightness, back pain, dyspnea, drug fever, or chills.
Severe reactions characterized by hypotension, bronchospasm, or generalized rash/erythema, have occurred within a few minutes following the initiation of infusion of docetaxel as a single agent. Severe symptoms were observed in 4% of the patients treated for various tumor types; however, 1.2% (25 of 2045) had immediate discontinuation of treatment. All hypersensitivity reactions resolved after discontinuation of the infusion and appropriate therapy.
Infusion Site Reactions: Infusion site reactions occurred in 6% of the patients treated with docetaxel as a single agent for various tumor types, and were generally mild. These reactions included skin sensitivities such as hyperpigmentation, inflammation, local erythema, redness or dryness of the skin, or swelling of the vein. Phlebitis or extravasation was observed less frequently.
Neurologic: Neurosensory symptoms characterized by paresthesia, dysesthesia or pain (including burning sensation) were reported in 49% of patients treated with docetaxel as a single agent for various tumor types and in 38% of patients treated for recurrent and/or metastatic SCCHN. Severe reactions were observed in less than 4% of the patients.
Neuromotor events (mainly characterized by weakness) were reported in 14% of patients treated with docetaxel as a single agent for various tumor types. These reactions were severe in 4% of patients.
When these symptoms occur, dosage must be adjusted. If symptoms persist, treatment should be discontinued (see 4.2 Recommended Dose and Dose Adjustment).
Patients who experienced neurotoxicity in clinical trials and for whom follow-up information on the complete resolution of the event was available had spontaneous reversal of symptoms with a median of 81 days from onset (range 0 to 741 days).
Other: Asthenia was reported by 62% of all patients and was considered severe in 13% of patients treated for various tumor types and in 21% of patients treated for recurrent and/or metastatic SCCHN. Arthralgias (5.5% to 9%) and myalgias (19%) were reported by patients but were generally considered to be mild to moderate.
Respiratory: Dyspnea has been reported.
DOCETAXEL INJECTION USP IN COMBINATION
The percentage of events related to combination therapy might be different from those related to monotherapy with docetaxel. Please refer to the following tables for adverse drug reactions related to different combination therapies.
- Adjuvant Treatment of Breast Cancer – Docetaxel in Combination with Doxorubicin and Cyclophosphamide
Adverse Drug Reactions during treatment: The following table presents the treatment emergent adverse events (TEAEs) possibly or probably related to treatment observed during treatment phase in the TAX316 study in which 744 patients were treated with 75 mg/m2 of docetaxel every 3 weeks in combination with 50 mg/m2 of doxorubicin and 500 mg/m2 of cyclophosphamide (TAC regimen) and 736 patients were treated with the combination of 500 mg/m2 of 5-fluorouracil, 50 mg/m2 of doxorubicin, and 500 mg/m2 of cyclophosphamide every 3 weeks (FAC regimen).
Table 6: Clinically Important Treatment Related Adverse Events in Patients in the TAX 316 Study
| Docetaxel (75 mg/m2) in combination with Doxorubicin (50 mg/m2) and Cyclophosphamide (500 mg/m2) [TAC regimen] N = 744 (%) | 5-fluorouracil (500 mg/m2) in combination with Doxorubicin (50 mg/m2) and Cyclophosphamide (500 mg/m2) [FAC regimen] N = 736 (%) | |||||||
|---|---|---|---|---|---|---|---|---|
| Adverse Event | Any | Grade 3 / 4 | Any | Grade 3 / 4 | ||||
| Body as a whole | ||||||||
| Abdominal pain | 7.3 | 0.5 | 3.3 | 0.0 | ||||
| Asthenia | 79.2 | 11.0 | 69.4 | 5.2 | ||||
| Fever in absence of infection | 43.1 | 1.2 | 13.2 | 0.0 | ||||
| Cardiovascular System | ||||||||
| Cardiac dysrhythmias | 3.9 | 0.1 | 2.9 | 0.3 | ||||
| Hypotension | 1.5 | 0.0 | 0.5 | 0.0 | ||||
| Phlebitis | 0.7 | 0.0 | 0.4 | 0.0 | ||||
| Syncope | 0.5 | 0.0 | 0.4 | 0.0 | ||||
| Vasodilatation | 20.3 | 0.9 | 15.9 | 0.4 | ||||
| Digestive System | ||||||||
| Anorexia | 19.9 | 2.2 | 16.4 | 1.2 | ||||
| Constipation | 22.6 | 0.4 | 21.5 | 1.2 | ||||
| Diarrhea | 30.9 | 3.2 | 23.5 | 1.0 | ||||
| Nausea | 80.4 | 5.1 | 87.4 | 9.5 | ||||
| Stomatitis | 69.1 | 7.1 | 52.6 | 2.0 | ||||
| Vomiting | 42.6 | 4.3 | 58.2 | 7.3 | ||||
| Hematologic | ||||||||
| Anemia | 91.5 | 4.3 | 71.7 | 1.6 | ||||
| Febrile neutropenia* | 24.7 | N/A | 2.5 | N/A | ||||
| Lymphedema | 0.3 | 0.0 | 0.0 | 0.0 | ||||
| Neutropenia | 71.4 | 65.5 | 82.0 | 49.3 | ||||
| Docetaxel (75 mg/m2) in combination with Doxorubicin (50 mg/m2) and Cyclophosphamide (500 mg/m2) [TAC regimen] N = 744 (%) | 5-fluorouracil (500 mg/m2) in combination with Doxorubicin (50 mg/m2) and Cyclophosphamide (500 mg/m2) [FAC regimen] N = 736 (%) | |||||||
|---|---|---|---|---|---|---|---|---|
| Adverse Event | Any | Grade 3 / 4 | Any | Grade 3 / 4 | ||||
| Thrombocytopenia | 39.4 | 2.0 | 27.7 | 1.2 | ||||
| Immune System | ||||||||
| Hypersensitivity reactions | 10.5 | 1.1 | 2.2 | 0.0 | ||||
| Infections and Infestations | ||||||||
| Infection | 27.2 | 3.2 | 17.4 | 1.4 | ||||
| Neutropenic infection** | 12.1 | N/A | 6.3 | N/A | ||||
| Metabolic and Nutritional Disorders | ||||||||
| Peripheral edema | 26.7 | 0.4 | 7.2 | 0.0 | ||||
| Weight gain or loss | 15.2 | 0.3 | 9.2 | 0.0 | ||||
| Musculoskeletal System | ||||||||
| Arthralgia | 15.1 | 0.4 | 5.7 | 0.3 | ||||
| Myalgia | 22.8 | 0.8 | 8.0 | 0.0 | ||||
| Nervous System | ||||||||
| Neuro-cerebellar | 1.1 | 0.1 | 0.8 | 0.0 | ||||
| Neuro-cortical | 2.8 | 0.3 | 3.9 | 0.3 | ||||
| Neuropathy motor | 2.8 | 0.0 | 1.5 | 0.0 | ||||
| Neuropathy sensory | 23.8 | 0.0 | 7.9 | 0.0 | ||||
| Respiratory System | ||||||||
| Cough | 3.1 | 0.0 | 2.2 | 0.1 | ||||
| Skin and Appendages | ||||||||
| Alopecia | 97.7 | N/A | 97.1 | N/A | ||||
| Nail disorders | 18.4 | 0.4 | 13.9 | 0.1 | ||||
| Skin toxicity | 18.4 | 0.7 | 10.9 | 0.3 | ||||
| Special Senses | ||||||||
| Conjunctivitis | 4.6 | 0.3 | 6.0 | 0.1 | ||||
| Lacrimation disorder | 9.8 | 0.1 | 6.4 | 0.0 | ||||
| Taste perversion | 27.4 | 0.7 | 15.1 | 0.0 | ||||
| Urogenital System | ||||||||
| Amenorrhea | 57.6 | N/A | 48.1 | N/A | ||||
* Febrile neutropenia was defined as grade ≥ 2 NCI term “fever in absence of infection” (oral temperature ≥ 38.1°C) concomitant (i.e., measured within 24 hours) with grade 4 neutropenia (ANC < 0.5 x 10⁹/L), requiring intravenous antibiotics and/or hospitalization. ** Neutropenic infection was defined as grade ≥ 2 NCI term “infection” concomitant (i.e., measured within 24 hours) with grade ≥ 3 neutropenia (ANC < 1.0 x 10⁹ /L). | ||||||||
During the treatment period, of the 744 patients treated with TAC in the TAX316 study, 33.1% experienced severe TEAEs possibly or probably related to treatment compared to 22.1% of the 736 patients treated with FAC. Dose reductions due to hematologic toxicity occurred in 1% of cycles in the TAC arm compared to 0.1% of cycles in the FAC arm. Six percent of patients treated with TAC discontinued treatment due to adverse events, compared to 1.1% treated with FAC; fever in the absence of infection and allergy being the most common reasons for withdrawal among TAC-treated patients. Two TAC-treated patients died within 30 days of their last study treatment; 1 death was considered to be related to study drug. Two FAC-treated patients died within 30 days of their last study treatment; 1 death was considered to be related to study drug.
Adverse Drug Reactions during follow-up: The follow-up period was defined as the period of time beginning after the end of chemotherapy visit and ending at the end of the 10-year follow-up period. A final analysis of the TAX316 study was performed, with an actual median follow-up of 96 months. Patients were followed until the initiation of further anti-cancer therapy, until lost to follow-up, or until the end of the 10-year follow-up period.
- Persistent TEAEs: The most common TEAEs that were first documented during the treatment period and persisted into the follow-up period, regardless of causal relationship, were alopecia (TAC: 687 patients; FAC: 645 patients), asthenia (TAC: 236 patients; FAC: 180 patients), amenorrhea (TAC: 202 patients; FAC: 136 patients), hot flush (TAC: 129 patients; FAC: 109 patients), edema peripheral (TAC: 119 patients; FAC: 23 patients), nail disorder (TAC: 106 patients; FAC: 79 patients), weight increased (TAC: 89 patients; FAC: 61 patients), and peripheral sensory neuropathy (TAC: 84 patients; FAC: 15 patients). Among TEAEs that persisted into the follow-up period in >1% of patients, the majority of events resolved.
- Ongoing TEAEs: TEAEs that were reported as ongoing at the end of the follow-up period include amenorrhea (TAC: 121 patients; FAC: 86 patients), alopecia (TAC: 29 patients; FAC: 16 patients), asthenia (TAC: 29 patients; FAC: 16 patients), hot flush (TAC: 38 patients; FAC: 43 patients), increased weight (TAC: 33 patients; FAC: 25 patients), peripheral sensory neuropathy (TAC:10 patients; FAC: 2 patients), arthralgia (TAC: 8 patients; FAC: 2 patients), lymphedema (TAC: 6 patients; FAC: 1 patient), myalgia (TAC: 6 patients; FAC: 0 patients) and dyspnea (TAC: 4 patients; FAC: 0 patients).
AEs that started or worsened during follow-up: During the follow-up period, 13.8% of TAC patients and 11.3% of FAC patients experienced at least one grade 3-4 adverse event that started or worsened during the follow-up period. The most common severe adverse events that started or worsened during follow-up include cardiac failure congestive (TAC: 26 patients; FAC: 17 patients), hot flush (TAC: 25 patients; FAC: 10 patients) and increased weight (TAC: 9 patients; FAC: 7 patients). The most common AEs that started or worsened during the follow-up period include hot flush (TAC: 177 patients; FAC: 200 patients), skin disorder (TAC: 151 patients; FAC: 157 patients) and amenorrhea (TAC: 79 patients; FAC: 99 patients). AEs that started or worsened during follow-up and remained ongoing at the end of the follow-up include amenorrhea (TAC: 46 patients; FAC: 50 patients), hot flush (TAC: 46 patients; FAC: 64 patients), weight
- patients), telangiectasia (TAC: 8 patients; FAC: 9 patients), pulmonary fibrosis (TAC: 10 patients; FAC: 9 patients), menstruation irregular (TAC: 7 patients; FAC: 8 patients), edema peripheral (TAC: 8 patients; FAC: 6 patients), and edema (TAC: 3 patients; FAC: 0 patients).
Fever and Infection: Treatment-related fever in the absence of infection was seen in 43.1% (Gr 3/4: 1.2%) of TAC-treated patients and in 13.2% (Gr 3/4: 0.0%) of FAC-treated patients. Treatment related infection was seen in 27.2% (Gr 3/4: 3.2%) of TAC-treated patients and in 17.4% (Gr 3/4: 1.4%) of FAC-treated patients. There were no septic deaths in either treatment arm. G-CSF was used as treatment or secondary prophylaxis in 29.2% of TAC-treated patients compared to 5.6% of FAC-treated patients.
Gastrointestinal events: In addition to gastrointestinal events reflected in the above table, 7 patients in the TAC treatment arm and 1 patient in the FAC treatment arm were reported to have treatment-related colitis/enteritis/large intestine perforation. Two of the 7 TAC-treated patients required treatment discontinuations.
Cardiovascular events: During the treatment period, more cardiovascular events were reported in the TAC arm than in the FAC arm: treatment-related dysrhythmias, all grades (3.9% vs 2.9%), treatment-related hypotension, all grades (1.5% vs 0.5%) and clinically significant treatment-emergent congestive heart failure (CHF), cardiac function grade 3-4 (1.6% vs 0.5%). One TAC-treated patient died due to heart failure. While left ventricular ejection fraction (LVEF) was measured at baseline as a study requirement in the TAX316 study, repeat measurements were not performed unless considered clinically relevant by the investigator. Of the patients with repeat LVEF assessment, 14/66 (21%) in the TAC treatment group and 4/48 (8.3%) in the FAC treatment group were reported to have LVEF declines to levels below the lower limit of normal. Twenty-six patients in the TAC group developed CHF during the study period, with most cases reported in the follow-up period. CHF lead to death in 2 TAC patients and in 4 FAC patients during follow-up period. The risk of CHF is higher in the TAC group in the first year.
Acute Myeloid Leukemia/Myelodysplastic Syndrome: At a median follow-up time of 96 months, 4 of 744 patients treated with TAC and 1 of the 736 patients treated with FAC were diagnosed with AML. MDS was reported in 2 TAC patients and in 1 FAC patients. In two of the TAC-associated AML cases, abnormalities of chromosome 11 were present. In one of the TAC-associated MDS case, the chromosome abnormality t(11; 14)(q23;q24) was present. One TAC patient died due to AML during the follow-up period.
- Locally-Advanced and/or Metastatic Breast Cancer – Docetaxel in Combination with Doxorubicin
The following two tables show data from a combination study with docetaxel and doxorubicin in patients with locally advanced and/or metastatic breast cancer. In this study, 258 patients received 75 mg/m2 of docetaxel with 50 mg/m2 of doxorubicin.
Table 7: Summary of Adverse Events Possibly or Probably Related to Study Treatment in Patients with Locally Advanced and/or Metastatic Breast Cancer Receiving Docetaxel in Combination with Doxorubicin
Docetaxel in combination (75 mg/m²) with Doxorubicin (50 mg/m2) N=258 (%) | |
|---|---|
| Alopecia | 94.6 |
Arthralgia -All Grades -Severe | 5.4 0.4 |
Asthenia -All Grades -Severe | 54.7 8.1 |
Cutaneous -All Grades -Grades III-IV | 13.6 0 |
Fever In Absence Of Infection -All Grades -Grades III-IV | 50.4* 0.4* |
Fluid Retention -All Grades -Severe | 35.7 1.2 |
Gastrointestinal Nausea (All) -Severe (Grades III-IV) Diarrhea (All) -Severe (Grades III-IV) Vomiting (All)
| 64.0 5.0 45.7 6.2 45.0 5.0 |
Hypersensitivity Reactions -All Grades -Severe | 4.7 1.2 |
| Infusion Site Reaction |
Docetaxel in combination (75 mg/m²) with Doxorubicin (50 mg/m2) N=258 (%) | |||
|---|---|---|---|
| -All Grades | 3.5 | ||
Myalgia -All Grades -Severe | 8.5 0 | ||
Nail Changes -All Grades -Severe | 20.2 0.4 | ||
Neuromotor -All Grades -Grades III-IV | 2.3 0.4 | ||
Neurosensory -All Grades -Grade III | 30.2 0.4 | ||
| Non-Septic Death | 2.3 | ||
| Septic Death | 0 | ||
Stomatitis -All Grades -Grades III-IV | 58.1 7.8 | ||
| *In study TAX 306 (n=213), it included febrile neutropenia. | |||
Table 8: Summary of Hematologic Adverse Events Possibly or Probably Related to Study Treatment in Patients with Locally Advanced and/or Metastatic Breast Cancer Receiving Docetaxel in Combination with Doxorubicin
Docetaxel in combination (75 mg/m2) with Doxorubicin (50 mg/m2) N=258 (%) | |
|---|---|
Anemia < 11 g/dL -Grades III-IV < 8 g/dL | 96.1 9.4 |
| Febrile Neutropenia | 34.1 |
Infection -All Grades -Grades III-IV | 35.3 7.8 |
Leukopenia < 4,000 cells/mm3 -Grade IV < 1,000 cells/mm3 | 99.6 53.5 |
Neutropenia < 2,000 cells/mm3 -Grade IV < 500 cells/mm3 | 99.2 91.7 |
| Thrombocytopenia < 100,000 cells/mm3 | 28.1 |
| -Grade IV | 0.8 |
|---|
Locally Advanced and/or Metastatic Breast Cancer – Docetaxel in Combination with
Capecitabine
The following text and table provide data for the combination study with docetaxel and capecitabine in 506 patients with locally advanced and/or metastatic breast cancer. In the Docetaxel-capecitabine combination arm (251 patients), the treatment was capecitabine administered orally 1250 mg/m2 twice daily as intermittent therapy (2 weeks of treatment followed by one week without treatment) for at least 6 weeks and Docetaxel administered as a 1-hour intravenous infusion at a dose of 75 mg/m2 on the first day of each 3 week cycle for at least 6 weeks. In the monotherapy arm (255 patients), docetaxel was administered as a one-hour intravenous infusion at a dose of 100 mg/m2 on the first day of each 3-week cycle for at least 6 weeks. The mean duration of treatment was 129 days in the combination arm and 98 days in the monotherapy arm. A total of 66 patients (26%) in the combination arm and 49 (19%) in the monotherapy arm withdrew from the study because of adverse events. The percentage of patients requiring dose reductions due to adverse events were 65% in the combination arm and 36% in the monotherapy arm. The hospitalization rate for treatment-related adverse events was 28.7% in the combination arm and 26.3% in the monotherapy arm.
Table 9: Adverse Events Considered Related to Treatment in ≥ 5% of Patients Participating in the Combination Study of Docetaxel and Capecitabine in Patients with Locally advanced and/or Metastatic Breast Cancer
| Adverse Event | Capecitabine 1250 mg/m2/bid (Intermittent Regimen) with Docetaxel 75 mg/m2/3 weeks (N=251) | Docetaxel 100 mg/m2/3 weeks (N=255) | |||||||||||||
|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|
Body System / Adverse Event | NCIC Grade | ||||||||||||||
Total % | Grade 3 % | Grade 4 % | Total % | Grade 3 % | Grade 4 % | ||||||||||
Gastrointestinal Stomatitis Diarrhea Nausea Vomiting Constipation Abdominal Pain Dyspepsia Abdominal pain upper Dry mouth | 67 64 43 33 14 14 12 9 5 | 17.1 13.5 6.4 3.6 1.2 2 - - 0.4 | 0.4 0.4 - 0.8 - - - - - | 43 45 35 22 12 9 5 6 4 | 4.7 5.4 2 0.8 - 0.8 0.4 - - | - 0.4 - - - - - - - | |||||||||
| Adverse Event | Capecitabine 1250 mg/m2/bid (Intermittent Regimen) with Docetaxel 75 mg/m2/3 weeks (N=251) | Docetaxel 100 mg/m2/3 weeks (N=255) | ||||||||||||||||
|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|
Body System / Adverse Event | NCIC Grade | |||||||||||||||||
Total % | Grade 3 % | Grade 4 % | Total % | Grade 3 % | Grade 4 % | |||||||||||||
Skin and Subcutaneous Hand-and-Foot Syndrome Alopecia Nail Disorder Dermatitis Rash, erythematous Nail discolouration Onycholysis Pruritis | 63 41 14 8 8 6 5 2 | 24.3 6 2 - 0.4 - 1.2 - | - - - - - - - - | 8 42 15 9 4 4 5 5 | 1.2 6.7 - 0.8 - 0.4 0.8 - | - - - - - - - - | ||||||||||||
General Pyrexia Asthenia Fatigue Weakness Pain in limb Lethargy Pain | 21 23 21 13 9 6 6 | 0.8 3.2 4.4 1.2 0.4 - - | - 0.4 - - - - - | 29 22 25 9 8 5 2 | 0.4 5.5 5.1 2 0.4 1.2 - | - - - - - - - | ||||||||||||
Neurological Taste disturbance Headache Paresthesia Dizziness Insomnia Peripheral neuropathy Hypoesthesia | 15 7 11 9 4 5 4 | 0.4 0.4 0.4 - - - - | - - - - - - - | 14 8 15 6 5 10 7 | 0.4 - 0.8 0.4 0.4 0.8 0.4 | - - - - - - - | ||||||||||||
Metabolism Anorexia Appetite decreased Dehydration | 12 10 8 | 0.8 - 2 | - - - | 10 4 5 | 0.8 - 0.4 | - - 0.4 | ||||||||||||
Eye Lacrimation increased | 12 | - | - | 5 | - | - | ||||||||||||
| Adverse Event | Capecitabine 1250 mg/m2/bid (Intermittent Regimen) with Docetaxel 75 mg/m2/3 weeks (N=251) | Docetaxel 100 mg/m2/3 weeks (N=255) | ||||||||||||||
|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|
Body System / Adverse Event | NCIC Grade | |||||||||||||||
Total % | Grade 3 % | Grade 4 % | Total % | Grade 3 % | Grade 4 % | |||||||||||
Musculoskeletal Arthralgia Myalgia Back pain | 11 14 7 | 1.2 1.6 0.8 | - - - | 18 24 6 | 2.4 2 0.8 | - - - | ||||||||||
Cardiac Edema, lower limb Edema, NOS Edema, peripheral | 14 4 4 | 0.8 - - | - - - | 12 5 5 | 1.2 - 0.4 | - 0.8 - | ||||||||||
Hematologic Neutropenia Neutropenic fever Anaemia | 17 16 13 | 4.8 2.8 2.8 | 10.8 13.1 0.8 | 16 21 11 | 2.7 4.7 3.9 | 11.8 16.1 - | ||||||||||
Respiratory Dyspnea Cough Sore throat Epistaxis | 7 6 11 5 | 0.8 0.4 1.6 0.4 | - - - - | 9 9 7 5 | 0.4 - 0.4 - | - - - - | ||||||||||
Infections and Infestations Oral candidiasis | 6 | 0.4 | - | 7 | 0.4 | - | ||||||||||
Cutaneous: Hand-and-foot syndrome was more common in patients in the combination therapy arm than in the Docetaxel monotherapy arm (63% vs. 8%).
Hematology: In 251 patients who received docetaxel in combination with capecitabine, 68% had grade 3 or 4 neutropenia, 2.8% had grade 3 or 4 thrombocytopenia and 9.6% had grade 3 or 4 anemia.
Hyperbilirubinemia: In 251 patients who received a combination of capecitabine and docetaxel, grade 3 and 4 hyperbilirubinemia occurred in 6.8% (n=17) and 2% (n=5), respectively.
Table 10: Patients with Laboratory Abnormalities Participating in the Combination Study of Docetaxel with Capecitabine in Patients with Locally-advanced and/or Metastatic Breast Cancer
| Adverse Event | Capecitabine 1250 mg/m2/bid (Intermittent Regimen) with Docetaxel 75 mg/m2/3 weeks (N=251) | Docetaxel 100 mg/m2/3 weeks (N=255) | |||||||||||
|---|---|---|---|---|---|---|---|---|---|---|---|---|---|
| Body System/Adverse Event | Total % | Grade 3 % | Grade 4 % | Total % | Grade 3 % | Grade 4 % | |||||||
Hematologic Leukopenia Neutropenia/Granulocytopenia Thrombocytopenia Anemia Lymphocytopenia | 91 86 41 80 99 | 37 20 2 7 48 | 24 49 7 3 41 | 88 87 23 83 98 | 42 10 1 5 44 | 33 66 2 <1 40 | |||||||
Hepatobiliary Hyperbilirubinemia | 20 | 7 | 2 | 6 | 2 | 2 | |||||||
Shown below by body system are the adverse events in < 5% of patients in the overall clinical trial safety database of 251 patients reported as related to the administration of capecitabine in combination with Docetaxel and that were clinically at least remotely relevant. In parentheses is the incidence of grade 3 and 4 occurrences of each adverse event.
Cardiovascular: supraventricular tachycardia (0.39), hypotension (1.20), venous phlebitis & thrombophlebitis (0.39), blood pressure increase (0.39), postural hypotension (0.80)
Gastrointestinal: hemorrhoids (0.39), ileus (0.39), necrotizing enterocolitis (0.39), esophageal ulcer (0.39), hemorrhagic diarrhea (0.80)
General: rigors (0.39), injection site infection (0.39), neuralgia (0.39)
Hematologic: agranulocytosis (0.39), prothrombin decreased (0.39)
Hepatobiliary: jaundice (0.39), abnormal liver function tests (0.39), hepatic failure (0.39), hepatic coma (0.39), hepatotoxicity (0.39)
Immune System: hypersensitivity (1.20)
Infection: neutropenic sepsis (2.39), lower respiratory tract infection NOS (0.39), pharyngitis (0.39), otitis media (0.39), sepsis (0.39), bronchopneumonia (0.39)
Neurological: ataxia (0.39), syncope (1.20), taste loss (0.80), polyneuropathy (0.39), migraine (0.39)
Renal: renal failure (0.39)
- Prostate Cancer – Docetaxel in Combination with Prednisone or Prednisolone
The following data are based on the experience of 332 patients, who were treated with Docetaxel 75 mg/m2 every 3 weeks in combination with prednisone or prednisolone 5 mg orally twice daily.
Table 11: Clinically Important Treatment-Related Adverse Events in Patients with Prostate Cancer who Received Docetaxel in Combination with Prednisone or Prednisolone (TAX 327)
| Adverse Event | Docetaxel 75 mg/m2 every 3 weeks with prednisone (or prednisolone) 5 mg twice daily (N=332) | ||||||
|---|---|---|---|---|---|---|---|
| Body System / Adverse Event | NCI Grade | ||||||
Total % | Grade 3/4 % | ||||||
| Alopecia | 65.1 | -- | |||||
| Allergic reactions | 6.9 | 0.6 | |||||
| Anemia | 66.5 | 4.9 | |||||
| Anorexia | 12.7 | 0.6 | |||||
| Arthralgia | 3.0 | 0.3 | |||||
| Cardiac left ventricular function decrease | 3.9 | 0.3 | |||||
| Cough | 1.2 | 0.0 | |||||
| Diarrhea | 24.1 | 1.2 | |||||
| Dyspnea | 4.5 | 0.6 | |||||
| Epistaxis | 3.0 | 0.0 | |||||
| Fatigue | 42.8 | 3.9 | |||||
| Febrile neutropenia | 2.7 | -- | |||||
| Fluid retention | 24.4 | 0.6 | |||||
| Infection | 12.0 | 3.3 | |||||
| Myalgia | 6.9 | 0.3 | |||||
| Nail changes | 28.3 | -- | |||||
| Nausea | 35.5 | 2.4 | |||||
| Neuropathy motor | 3.9 | 0.0 | |||||
| Neuropathy sensory | 27.4 | 1.2 | |||||
| Neutropenia | 40.9 | 32.0 | |||||
| Rash/Desquamation | 3.3 | 0.3 | |||||
| Adverse Event | Docetaxel 75 mg/m2 every 3 weeks with prednisone (or prednisolone) 5 mg twice daily (N=332) | |||
|---|---|---|---|---|
| Body System / Adverse Event | NCI Grade | |||
| Stomatitis/Pharyngitis | 17.8 | 0.9 | ||
| Taste disturbance | 17.5 | -- | ||
| Tearing | 9.3 | 0.6 | ||
| Thrombocytopenia | 3.4 | 0.6 | ||
| Vomiting | 13.3 | 1.2 | ||
Of the 332 patients treated with docetaxel every three weeks in the prostate cancer study (TAX 327), 208 patients were 65 years of age or greater and 67 patients were older than 75 years. In patients treated with docetaxel every three weeks, the incidence of anemia, infection, nail changes, anorexia, weight loss, regardless of relationship to docetaxel, occurred at rates ≥ 10% higher in patients who were 65 years of age or greater compared to younger patients. Fatigue, all grades, was one of the most commonly reported TEAEs, regardless of relationship to docetaxel, in patients treated with docetaxel every three weeks, but grade 3-4 were experienced in only 1.6% of subjects < 65 years old, 6.3% in those ≥ 65 years, and 10.4% in those ≥ 75 years old. Similarly, diarrhea, all grades, was also commonly reported, but the incidence of grade 3-4 diarrhea was much lower for each age category, 1.6%, 2.4% and 3.0% respectively. There was a similar pattern for the incidence of infection grade 3-4, in the three age categories the incidence was 4.0%, 6.7%, and 9.0%, respectively.
8.5 Post-Market Adverse Reactions
Cardiovascular:
Cases of venous thromboembolic events and myocardial infarction have been reported.
Ventricular arrhythmia (including sometimes fatal ventricular tachycardia, fibrillation and extrasystole) has been reported in patients treated with docetaxel in combination regimens including, but not limited to, doxorubicin, 5-fluorouracil and/or cyclophosphamide (see 7 WARNINGS AND PRECAUTIONS, Cardiovascular).
Cutaneous:
Cases of cutaneous lupus erythematosus, bullous eruptions such as erythema multiforme, severe cutaneous adverse reactions such as Stevens-Johnson syndrome, toxic epidermal necrolysis and acute generalized exanthematous pustulosis have been reported with docetaxel. Scleroderma-like changes usually preceded by peripheral lymphedema have been reported with docetaxel. In some cases, multiple factors such as concomitant infections, concomitant medications and underlying disease may have contributed to the development of these effects. Cases of permanent alopecia have been reported.
Fluid Retention:
Dehydration and pulmonary edema have been reported.
Gastrointestinal:
Cases of gastrointestinal perforation; dehydration as a consequence of gastrointestinal events, including enterocolitis and gastrointestinal perforation. Enterocolitis, including ischemic colitis, colitis and neutropenic enterocolitis have been reported; some cases resulted in fatal outcome.
Cases of ileus and intestinal obstruction have been reported.
General disorders and administration site conditions:
Injection site recall reactions (recurrence of skin reaction at a site of previous extravasation following administration of docetaxel at a different site) have been observed.
Hematologic:
Cases of acute myeloid leukemia (AML) and myelodysplastic syndrome (MDS) have been reported in association with docetaxel when used in combination with other chemotherapy agents and/or radiotherapy. Disseminated intravascular coagulation (DIC), often in association with sepsis, or multiorgan failure, has been reported.
Hepatic:
Cases of hepatitis and hepatic failure, sometimes fatal primarily in patients with pre-existing liver disorders, have been reported.
Hypersensitivity Reactions:
Cases of severe hypersensitivity reactions/anaphylactic shock have been reported. Cases of anaphylactic shock with a fatal outcome have been reported in patients who received premedication.
Hypersensitivity reactions/anaphylactic shock have been reported with docetaxel in patients who previously experienced hypersensitivity reactions/anaphylactic shock to paclitaxel.
Metabolism and nutrition disorders:
Cases of electrolyte imbalance have been reported. Serious cases of hyponatraemia have been reported, some associated with dehydration, vomiting and pneumonia. Hypokalaemia (including serious cases), hypomagnesaemia, and hypocalcaemia were observed, usually in association with gastrointestinal disorders and in particular with diarrhea. Tumor lysis syndrome, sometimes fatal, has been reported.
Musculoskeletal:
Myositis has been reported with docetaxel.
Neoplasms benign, malignant and unspecified (including cysts and polyps):
Second primary malignancies (frequency not known) including non-Hodgkin lymphoma and renal cancer, have been reported in association with docetaxel when used as a monotherapy and in combination with other anticancer treatments known to be associated with second primary malignancies. Acute myeloid leukemia and myelodyplastic syndrome have been reported (frequency uncommon) in pivotal clinical studies in breast cancer with TAC or FAC regimens.
Neurologic:
Cases of convulsion or transient loss of consciousness have been observed with docetaxel administration. These reactions sometimes appear during the infusion of the drug.
Ophthalmologic:
Cases of lacrimation with or without conjunctivitis have been reported and cases of lacrimal duct obstruction resulting in excessive tearing have been reported primarily in patients receiving other anti-tumor agents concomitantly.
Cases of transient visual disturbances (flashes, flashing lights, scotomata) typically occurring during drug infusion and in association with hypersensitivity reactions have been reported. These were reversible upon discontinuation of the infusion.
Cases of cystoid macular edema (CME) have been reported in patients treated with docetaxel (see 7 WARNINGS AND PRECAUTIONS). Based on a number of documented reports, including literature cases, an association between CME and docetaxel is considered to be reasonably well established. Features specific to this clinical entity (docetaxel-induced CME) may include an absence of vascular leakage with no other precipitating factors. Certain cases of CME were reversible upon discontinuation of docetaxel therapy, in some cases with initiation of appropriate treatment, while in other cases no further treatment was required.
Other:
Generalised and localised pain including chest pain without any cardiac or respiratory involvement.
Ototoxicity and Hearing disorders:
Ear and labyrinth disorders include cases of ototoxicity, hearing disorders and/or hearing loss which have been reported, including cases associated with other ototoxic drugs.
Renal:
Cases of renal insufficiency, including renal failure, have been reported in clinical trials with docetaxel, and they are typically associated with concomitant nephrotoxic drugs.
Respiratory:
Acute respiratory distress syndrome, interstitial pneumonia/pneumonitis, interstitial lung disease, lung infiltration, pulmonary fibrosis, respiratory failure and radiation recall phenomena have been reported, and have occasionally been associated with fatal outcome. Cases of radiation pneumonitis have been reported in patients receiving concomitant radiotherapy.
9 DRUG INTERACTIONS
9.4 Drug-Drug Interactions
Docetaxel is a CYP3A4 substrate. In vitro studies have shown that the metabolism of docetaxel may be modified by the concomitant administration of compounds, that induce, inhibit or are metabolised by (and thus may inhibit the enzyme competitively) CYP3A4 such as rifampin, cyclosporine, terfenadine, ketoconazole, erythromycin and troleandomycin. As a result, caution should be exercised when treating patients with these drugs as concomitant therapy since there is a potential for a significant interaction.
The exposure of docetaxel increased 2.2-fold when it was coadministered with ketoconazole, a potent inhibitor of CYP3A4. Protease inhibitors, particularly ritonavir, may increase the exposure of docetaxel. Concomitant use of docetaxel and drugs that inhibit CYP3A4 (such as ketoconazole, itraconazole, clarithromycin, indinavir, nefazodone, nelfinavir, ritonavir, saquinavir, telithromycin and voriconazole) may increase adverse reactions as a result of increased exposure to docetaxel and should be avoided. In patients receiving treatment with docetaxel, close monitoring for toxicity and a docetaxel dose reduction could be considered if systemic administration of a potent CYP3A4 inhibitor cannot be avoided.
Each intravenous administration of Docetaxel Injection USP (at 100 mg/m2) delivers approximately 1.81 g/m2 of alcohol. The alcohol content may alter the effects of other medicinal products. Central nervous system depression may be exacerbated and occur at a lower blood alcohol levels when Docetaxel Injection USP is taken along with other CNS depressants (e.g., diazepam or similar benzodiazepines). Some medications (e.g., pain relievers, sleep aids) may worsen alcohol intoxicating effects.
Docetaxel is highly protein-bound (> 95%). Although the possible in vivo interaction of Docetaxel with concomitantly administered medication has not been investigated formally, in vitro interactions with tightly protein-bound drugs, such as erythromycin, diphenhydramine, propranolol, propafenone, phenytoin, salicylate, sulfamethoxazole and sodium valproate did not affect protein binding of Docetaxel. Docetaxel did not influence the binding of digoxin.
The effect of daily oral prednisone administration on the pharmacokinetics of docetaxel administered with dexamethasone premedication prior to infusion has been evaluated in 42 patients treated for prostate cancer. No effect of prednisone on the pharmacokinetics of docetaxel was observed.
There is no evidence of a pharmacokinetic interaction between docetaxel and doxorubicin.
The pharmacokinetics of docetaxel given in combination with doxorubicin and cyclophosphamide, have been studied in 30 patients treated for advanced breast cancer. There was no evidence of a pharmacokinetic interaction between the three drugs.
A phase I study evaluating the effect of capecitabine on the pharmacokinetics of docetaxe1 and the effect of docetaxel on the pharmacokinetics of capecitabine was conducted in 26 patients with solid tumors. Capecitabine was found to have no effect on the pharmacokinetics of docetaxel (Cmax and AUC) and docetaxel has no effect on the pharmacokinetics of 5’-DFUR.
9.5 Drug-Food Interactions
Interactions with food have not been established.
9.6 Drug-Herb Interactions
Interactions with herbal products have not been established.
9.7 Drug-Laboratory Test Interactions
Interactions with laboratory tests have not been established.
10 CLINICAL PHARMACOLOGY
10.1 Mechanism of Action
Docetaxel is an antineoplastic agent, which acts by disrupting the microtubular network in cells that is essential for vital mitotic and interphase cellular functions. Docetaxel promotes the assembly of tubulin into stable microtubules while simultaneously inhibiting their disassembly. Docetaxel binds to free tubulin thereby decreasing the critical intracellular concentration of tubulin. The promoted polymerization of microtubules leads to the production of microtubule bundles without normal function and to the stabilization of microtubules, resulting in the inhibition of mitosis in cells. The binding of docetaxel to microtubules does not alter the number of protofilaments in the bound microtubules; in that, it differs from other spindle poisons.
Docetaxel was found to be cytotoxic in vitro against various murine and human tumor cell lines, and against freshly excised human tumor cells in clonogenic assays.
In addition, docetaxel was found to be active on a number of cell lines overexpressing the p-glycoprotein, which is encoded by the multidrug resistant gene.
10.2 Pharmacodynamics
In vitro, docetaxel is active against several murine and human cell lines at low concentrations ranging from 4 to 35 ng/mL in liquid medium. In head-to-head comparisons, docetaxel was generally more cytotoxic than paclitaxel (1-12 fold). Cross-resistance to docetaxel was studied in 11 cell lines overexpressing the Multi-Drug Resistance (MDR) gene and exposed to various anticancer agents. In six of them, IC50 values of docetaxel were identical for normal and resistant cells and therefore no cross-resistance was noted. Combination therapy of docetaxel with several reference antitumor drugs has been explored. No synergy was detected with cisplatin or doxorubicin. Additive effects were noted with vincristine. Synergistic effects were obtained with cyclophosphamide and 5-fluorouracil (5-FU).
In vivo, docetaxel was administered i.v. against tumors grafted in distal sites (generally subcutaneously), and several tumors were treated at advanced and metastatic stages. Docetaxel was able to induce the complete regressions of several advanced grafted murine solid tumors. The activities were dose-related and obtained at dosages not toxic for the mice. Experimental antitumor activity was also tested against a panel of human tumor xenografts. Docetaxel exerted curative activities against ovarian and breast tumors and melanoma.
In human cancer xenograft models, capecitabine demonstrated a synergistic effect in combination with docetaxel, which may be related to the upregulation of thymidine phosphorylase by docetaxel.
10.3 Pharmacokinetics
The pharmacokinetics of docetaxel have been extensively studied in animals. In summary, it can be concluded that docetaxel is characterised by a multiphasic plasma kinetic profile, has good tissue distribution, and is extensively metabolised in the liver.
After intravenous administration, docetaxel is distributed to all tissues and organs except the brain where extremely low levels were found. It is also detected in the foetus, tumour tissue and milk. It is eliminated very rapidly, although at a slower rate from tumour tissue than from normal tissue. It is excreted mainly in the faeces after undergoing hepatic metabolism and excretion. Urinary excretion is very limited. The drug is not markedly absorbed from the gastrointestinal tract.
The studies conducted in vivo (identification of major metabolites in excreta) and in vitro (liver microsome preparations of various species) demonstrated that monooxygenase enzymes, in particular cytochrome P450 3A, play a leading role in docetaxel metabolism while conjugation reactions are very limited.
In humans, the metabolic profile of docetaxel is comparable to that of the species used in the toxicity studies. At doses of 70-115 mg/m2, the kinetic profile of docetaxel is dose-independent and consistent with a three-compartment pharmacokinetic model, with half-lives for the α, β and ϒ phases of 4 min, 36 min and 11.1 h, respectively. An additional study assessing the pharmacokinetics of docetaxel at similar doses (75 – 100 mg/m2) in patients, but over a longer time interval (over 22 days) found a longer mean terminal elimination half-life between 91 and 120 h. The late phase is due, in part, to a relatively slow efflux of docetaxel from the peripheral compartment.
Docetaxel is more than 95% protein bound, to α1-acid glycoprotein, albumin and lipoproteins, with high binding affinity for α1- acid glycoprotein. Dexamethasone does not affect the protein binding of docetaxel.
Mean values for total body clearance and steady state volume of distribution were 21 L/h/m2 and 113 L, respectively.
A study in cancer patients administered 14C-docetaxel revealed that docetaxel was eliminated in the urine and feces within seven days. The urinary and fecal excretion accounted for about 6% and 75% of the administered radioactivity, respectively. About 80% of the radioactivity recovered in feces is excreted during the first 48 hours as one major inactive metabolite and 3 minor inactive metabolites and 2.7% of unchanged drug.
A population pharmacokinetic analysis has been performed in patients receiving docetaxel. Pharmacokinetic parameters estimated by the model were very close to those estimated from Phase I studies. The pharmacokinetics of docetaxel were not altered by the age or sex of the patient, but by liver hepatic impairment. In a study in patients with varying degrees of hepatic impairment (due to malignancies), decreased clearance (by 47% on average) of docetaxel was observed in patients with hepatic impairment (bilirubin > ULN or ALT/AST > 1.5 but ≤ 5 x ULN concurrent with alkaline phosphatase > 2.5 but ≤ 5 x ULN) when compared to those with normal hepatic function. Serum free docetaxel was not measured in this study.
The effect of daily oral prednisone administration on the pharmacokinetics of docetaxel administered with dexamethasone premedication prior to infusion has been evaluated in 42 patients treated for prostate cancer. No effect of prednisone on the pharmacokinetics of docetaxel was observed.
11 STORAGE, STABILITY AND DISPOSAL
Stability
After dilution in 0.9% sodium chloride or 5% dextrose, chemical and physical in-use stability has been demonstrated for 4 hours when stored between 2°C and 25°C. The Docetaxel infusion solution should be used within 4 hours, including the 1-hour intravenous administration.
Docetaxel Injection USP maintains microbial, chemical and physical stability when used as a multidose vial that is punctured 3 times for a period of 28 days.
Storage
Store the unopened vials between 2°- 25°C. Retain in the original package to protect from light and freezing.
After first needle entry, the multidose vials must be stored at 2°C to 8oC and protected from light and freezing.
12 SPECIAL HANDLING INSTRUCTIONS
Docetaxel Injection USP is a cytotoxic anticancer drug and, as with other potentially toxic compounds, caution should be exercised when handling and preparing Docetaxel Injection USP solutions. The use of gloves is recommended.
If Docetaxel Injection USP should come into contact with the skin, immediately and thoroughly wash with soap and water. If Docetaxel Injection USP should come into contact with mucosa, immediately and thoroughly wash with water.
Procedures for proper handling and disposal of anticancer drugs should be considered. Several guidelines on this subject have been published. There is no general agreement that all of the procedures recommended in the guidelines are necessary or appropriate.
PART II: SCIENTIFIC INFORMATION
13 PHARMACEUTICAL INFORMATION
Drug Substance
Proper name: Docetaxel (anhydrous)
Chemical name: (2R,3S)-N-carboxy-3-phenylisoserine, N-tert-butyl ester,13-ester with 5β-20-epoxy-1,2α,4,7β,10β,13α-hexahydroxytax-11-en-9-one 4-acetate 2-benzoate
Molecular formula and molecular mass: C43H53NO14, 807.88
Structural formula:
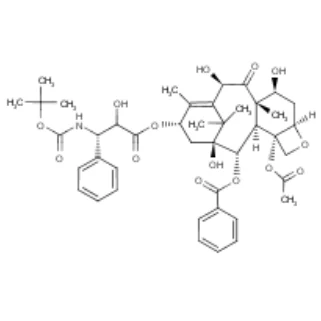
Physicochemical properties:
Description: White to almost white powder; the melting point is about 177.8°C to 182.8°C.
Solubility: Practically insoluble in water
14 CLINICAL TRIALS
Comparative Pharmacokinetic Study DOE 061
A phase I, double-blinded, randomized multi-center, three-period, three-treatment, crossover study to compare the intravenous pharmacokinetic and safety characteristics of European Taxotere® and American Taxotere® with Hospira Docetaxel Injection (HDI*) administered at a therapeutic dose in cancer patients. Each patient received Hospira Docetaxel Injection and Taxotere® EU (TEU) and Taxotere® US (TUS) in random order once every three weeks for the first three cycles of docetaxel monotherapy. Physicochemical studies performed by Hospira have shown that the Taxotere® Canadian Reference Product is essentially the same as Taxotere® US (TUS) and Taxotere® EU (TEU) in all respects.
The dose used in the comparative intravenous study was 60 to 100 mg/m2 given as a 1-hr intravenous infusion. Blood was collected predose, at 30 and 58 min during the 60-min
*HDI and Docetaxel Injection USP are the same product. At the time of the study, Hospira was the market authorization holder of the product.
infusion, and then at 65, 70 and 90 min, and 2 , 3 , 5, 7, 24 and 48 hr on Day 1 of each of the 3 cycles. Docetaxel in plasma was measured using a fully validated LC/MS/MS method with a limit of quantitation of 2 ng/mL. A sufficient number of quantifiable plasma docetaxel concentrations existed in 25 subjects in the HDI period and at least one other study treatment period to be included in the PK analyses.
AUCT, AUCI and t1/2 are presented for total docetaxel in Table 12. These results are normalised to a dose of 100 mg/m2.
Table 12: Primary and Secondary pharmacokinetic analyses: based on total docetaxel concentration
Docetaxel 100 mg/m2 | |||||||
| Parameter | Hospira Docetaxel Injection (HDI) | European Taxotere (TEU) | US Taxotere (TUS) | Adjusted Geometric Mean Ratio | 90% Confidence Interval | ||
| HDI/TEU | HDI/TUS | HDI/TEU | HDI/TUS | ||||
| N | 25 | 23 | 25 | ||||
AUCT a (h·ng/mL) | 3845 | 4241 | 4422 | 0.91 | 0.87 | 0.82-1.00 | 0.79-0.96 |
| N | 24 | 21 | 24 | ||||
AUCI a (h·ng/mL) | 4276 | 4548 | 4743 | 0.94 | 0.90 | 0.85-1.04 | 0.82-0.99 |
| N | 24 | 21 | 24 | ||||
t ½ b (h) | 24.0 (30.4%) | 20.5 (30.0%) | 21.0 (21.0%) | ||||
a Geometric mean
b Arithmetic mean (CV)
Breast Cancer
- Adjuvant Treatment of Breast Cancer
Data from a multicenter unblinded randomized trial support the use of docetaxel for the adjuvant treatment of patients with operable node-positive breast cancer. After stratification according to the number of positive lymph nodes (1-3, 4+), 1491 patients were randomized to receive either docetaxel 75 mg/m2 administered 1-hour after doxorubicin 50 mg/m2 and cyclophosphamide 500 mg/m2 (TAC arm), or doxorubicin 50 mg/m2 followed by fluorouracil 500 mg/m2 and cyclophosphamide 500 mg/m2 (FAC arm). Both regimens were administered once every 3 weeks for 6 cycles. Docetaxel was administered as a 1-hour infusion, all other drugs were given as IV bolus on day 1. Prophylactic antibiotic therapy was compulsory for subjects treated with docetaxel (TAC). Ciprofloxacin was recommended starting day 5 of each cycle. Subjects on FAC were given prophylactic antibiotics for all cycles following an episode of febrile neutropenia or infection. G-CSF was administered as secondary prophylaxis to patients in both treatment groups who experienced febrile neutropenia, prolonged neutropenia or neutropenic infection. In both arms, after the last cycle of chemotherapy, patients with positive estrogen and/or progesterone receptors received tamoxifen 20 mg daily for up to 5 years. Adjuvant radiation therapy was prescribed according to guidelines in place at participating institutions and was given to 69% of patients who received TAC and 72% of patients who received FAC.
The primary efficacy variable was disease-free survival (DFS) and the main secondary efficacy variable was overall survival.DFS was defined as the time interval between the date of randomization and the date of occurrence of local, regional or metastatic relapse, or the date of second primary cancer or death from any cause, whichever occurs first. After a protocol amendment, further to the Independent Data Monitoring Committee (IDMC) recommendation, subjects who received additional antitumor therapy without evidence of relapse for whatever reason (e.g., intolerance to randomized therapy, withdrawal of consent after randomization) were not to be counted as DFS events. In the original study protocol such subjects were to be counted as events. This involved a total of 81 (5.4%) subjects; 57 (7.7%) subjects randomized to the TAC group and 24 (3.2%) to the FAC group. An interim analysis was planned for 3 years after recruitment of 50% of the subjects using the Peto stopping rule. The final analysis was to be done after 590 events using a 0.05 significance level.
Results presented below are based on a second interim analysis. The first interim analysis (conducted with a median follow-up of 33 months) showed that TAC was associated with a 32% relapse risk reduction (HR 0.68, 95% Cl 0.54-0.86) but the corresponding p-value of 0.0011 did not meet the Peto stopping rule boundary which required the p-value to be less than or equal to 0.001. The independent data monitoring committee (IDMC) concluded that the study protocol should be amended to include a second interim analysis after 400 DFS had been recorded overall, in addition to the protocol-specified final analysis at 590 DFS events. The significance level to be used for the final analysis was revised to 0.048.
Subjects had a median age of 49 years (range 23-70), 49% of subjects were pre-menopausal, and 76% had positive estrogen and/or progesterone receptors. The six cycles of treatment were completed as per protocol in 91.1% and 95.3% of TAC and FAC-treated subjects, respectively.
The second interim analysis was performed with a median follow up of 55 months. Significantly longer disease-free survival for the TAC arm compared to the FAC arm was demonstrated. TAC-treated patients had a 28% relative reduction in the risk of relapse compared to those treated with FAC (hazard ratio=0.72, 95% CI (0.59-0.88) p=0.001, stopping boundary 0.001). This corresponds to an absolute difference in risk of relapse of 8.5% at 4 years. Overall survival was also significantly longer in the TAC arm with TAC-treated patients having a 30% relative reduction in the risk of death compared to FAC (hazard ratio= 0.70, 95% CI (0.53-0.91), p=0.008). This corresponds to an absolute difference in risk of death of 4.0% at 4 years.
Patient subsets according to prospectively defined major prognostic factors were analyzed (see table 13 below):
Table 13: Subset Analyses-Adjuvant Breast Cancer Study of TAC vs. FAC (Intent-to-Treat Analysis)
| Patient subset | Number of patients | Disease Free Survival | Overall Survival | ||
|---|---|---|---|---|---|
| Hazard ratio* | 95% CI | Hazard ratio* | 95% CI | ||
Number of positive nodes Overall 1-3 4+ | 745 467 278 | 0.72 0.61 0.83 | (0.59-0.88) (0.46-0.82) (0.63-1.08) | 0.70 0.45 0.94 | (0.53-0.91) (0.29-0.70) (0.66-1.33) |
Receptor status Positive Negative | 567 178 | 0.72 0.69 | (0.56-0.92) (0.49-0.97) | 0.69 0.66 | (0.48-1.00) (0.44-0.98) |
Her-2-neu status Positive Negative | 155 475 | 0.60 0.76 | (0.41-0.88) (0.59-1.00) | 0.74 0.63 | (0.45-1.20) (0.44-0.91) |
| *a hazard ratio of less than 1 indicates that TAC is associated with a longer disease free survival and overall survival compared to FAC. | |||||
The beneficial effect of TAC was seen in both hormone receptor positive and negative patients, and in patients with 1 to 3 positive nodes. However, a beneficial effect of TAC in patients with 4 or more positive lymph nodes was not observed with a median follow-up of 55 months; in the 4+ nodes stratum, the risk reduction in both disease free survival and overall survival associated with TAC was not significantly different from zero.
A final analysis was performed with an actual median follow-up of 96 months. Significantly longer DFS for the TAC arm compared to the FAC arm was demonstrated. TAC-treated patients had a 20.5% relapse risk reduction compared to those treated with FAC (HR = 0.80, 95% CI
(0.68-0.93), p = 0.0043). This corresponds to an absolute difference in risk of relapse of 6% at 10 years.
Overall survival at 10 years was also significantly increased in the TAC arm, with the TAC-treated patients having a 25.8 % relative reduction in risk of death compared to FAC (HR = 0.74, 95% CI (0.61-0.90), p=0.002). This corresponds to an absolute reduction of the risk of death of 7% at 10 years. However, the positive benefit for TAC in patients with 4+ nodes was not fully demonstrated since the differences in DFS and OS between TAC and FAC remained not statistically significant in the 4+ nodes stratum at 10 years.
Patient subsets according to prospectively defined major prognostic factors were analyzed (see Table 14 below):
Table 14: Subset Analyses-Adjuvant Breast Cancer Study of TAC vs. FAC (Intent-to-Treat Analysis) at 96 months follow-up
| Patient subset | Number of patients | Disease Free Survival | Overall Survival | |||
|---|---|---|---|---|---|---|
| TAC | FAC | |||||
| Hazard ratio* | 95% CI | |||||
| P value | ||||||
| Hazard ratio* | 95% CI | |||||
| P value | ||||||
Number of positive nodes Overall 1-3 4+ | 745 467 278 | 746 459 287 | 0.80 0.72 0.87 | (0.68-0.93) (0.58-0.91) (0.70-1.09) | ||
0.0043 0.0047 0.2229 | 0.74 0.62 0.87 | (0.61-0.90) (0.46-0.82) (0.67-1.12) | ||||
0.0020 0.0008 0.2746 | ||||||
Receptor status Positive Negative | 567 178 | 565 181 | 0.84 0.66 | (0.70-1.01) (0.49-0.89) | 0.76 0.69 | (0.60-0.96) (0.49-0.96) |
Her-2-neu status Positive Negative | 155 475 | 164 468 | 0.60 0.88 | (0.43-0.83) (0.72-1.08) | 0.66 0.79 | (0.45-0.96) (0.61-1.01) |
| * a hazard ratio of less than 1 indicates that TAC is associated with a longer disease free survival and overall survival compared to FAC | ||||||
- Locally Advanced or Metastatic Breast Cancer
Six phase II studies were conducted in patients with locally advanced or metastatic breast carcinoma. Among the 325 patients recruited in these studies, 190 patients had progressive disease with anthracycline therapy (anthracycline refractory patients). In these clinical trials, Docetaxel was administered at a 100 mg/m2 dose given as a one-hour infusion every 3 weeks.
The overall response rate (ORR) for evaluable patients was 43.3% with 3.1% complete responses (CR). The median duration of response of the previously treated and the anthracycline refractory patients was 28 and 26 weeks, respectively. The mean time to progression was 18 weeks for the previously treated and the anthracycline refractory patients. The median survival time of the previously treated and the anthracycline refractory patients was 11 and 10 months, respectively.
Two phase III clinical trials were performed involving a total of 326 metastatic breast cancer patients who previously failed to respond to alkylating agents, and 392 metastatic breast cancer patients who previously failed to respond to anthracycline agents. These patients were randomized to receive either docetaxel at the dose of 100 mg/m2 administered every 3 weeks or comparator agents.
In the clinical trial with patients who previously failed to respond to alkylating agents, docetaxel was compared to doxorubicin (75 mg/m2 every 3 weeks). The results demonstrated that Docetaxel had a statistically significant higher response rate than doxorubicin (52% versus 37.4%, p= 0.012), a statistically significant quicker time to onset of antitumor response (12 weeks versus 23 weeks, p= 0.007), and also a longer median time to progression (27 weeks versus 23 weeks). The median overall survival was 14.7 months in docetaxel patients versus 14.3 months in doxorubicin patients.
Additionally in the clinical trial with patients who previously failed to respond to anthracycline agents, docetaxel was compared to the combination of Mitomycin C and Vinblastine (12 mg/m2 every 6 weeks and 6 mg/m2 every 3 weeks). The results demonstrated that docetaxel had a statistically significant higher response rate that Mitomycin C and Vinblastine (33% versus 12.3%, p<0.0001), a statistically significant longer median time to progression (19 weeks versus 11 weeks, p= 0.0004) and also a statistically significant longer overall survival (11.4 months versus 8.7 months, p= 0.01).
Docetaxel in Combination with Doxorubicin:
One phase III study was conducted in previously untreated patients with metastatic breast cancer. The combination docetaxel (75 mg/m2) and doxorubicin (50 mg/m2) was compared to the combination of cyclophosphamide (600 mg/m2) and doxorubicin (60 mg/m2). Both regimens were administered once every 3 weeks. The results demonstrated that docetaxel in combination with doxorubicin had a statistically significantly longer median time to progression than the combination cyclophosphamide and doxorubicin (37.3 weeks versus 31.9 weeks, p=0.0138), a statistically significant higher overall response rate (59.3% versus 46.5%, p= 0.009) and also a statistically significantly longer median time to treatment failure (25.6 weeks versus 23.7 weeks, p= 0.0479). In this trial, the incidence and severity of cardiac toxicity was lower although not statistically significant in the doxorubicin/docetaxel arm versus the doxorubicin/cyclophosphamide arm.
Serious adverse events (SAE’s) were observed in 55.9% of AT-treated patients compared with 33.8% of AC-treated patients, that is, the incidence of SAE’s among AT-treated patients was 1.67 times higher than that among AC-treated patients. The following treatment-related SAE’s were more frequent in patients receiving AT than in patients receiving AC: febrile neutropenia (31.5% versus 9.0%, 3.5 times more common), vomiting (5.6% versus 2.4%, twice as common), diarrhea (4.7% versus 0.5%, 10 times more common) and nausea (3.3% versus 1.0%, 3 times more common). Other treatment-related grade 3 / 4 toxicities that were more frequent in AT-treated patients than in AC-treated patients included stomatitis (8.5% versus 6.7%, 1.3 times more common), asthenia (8.5% versus 2.4%, 3 times more common), pain (2.8% versus 0), allergy (1.4% versus 0), and anorexia, constipation, nail disorder and peripheral edema (all 0.5% versus 0). On the other hand, AC-treated patients had a higher incidence of severe anemia compared with AT-treated patients (15.8% versus 8.5%, twice as common), and, in addition, a higher incidence of severe cardiac toxicity: congestive heart failure (3.8% versus 2.8%, 1.5 times more common), absolute LVEF decrease of at least 20% (13.1 % versus 6.1%, twice as common), absolute LVEF decrease of at least 30% (6.2% versus 1.1%, 6 times more common). Toxic death occurred in 1 patient in the AT arm (congestive heart failure) and in 4 patients in the AC arm (1 due to septic shock and 3 due to congestive heart failure).
Docetaxel in Combination with Capecitabine:
Docetaxel has been evaluated in breast cancer clinical trials in combination with capecitabine (Xeloda). The dose of capecitabine used in combination with docetaxel in the phase III clinical trial was based on the results of a phase I study, where a range of doses of docetaxel given every 3 weeks in combination with an intermittent regimen of capecitabine were evaluated. The combination dose regimen was selected based on the tolerability profile of the 75 mg/m2 every 3 weeks of docetaxel in combination with 1250 mg/m2 twice daily for 14 days of capecitabine administered every 3 weeks. The approved dose of 100 mg/m2 of docetaxel administered every 3 weeks was the control arm of the phase III study.
As shown in the following Table, capecitabine in combination with docetaxel resulted in statistically significant improvement in time to disease progression, overall survival and objective response rate.
Health Related Quality of Life (HRQoL) was assessed using EORTC QLQ-C30 (version 2) and Breast Cancer Module of the EORTC (BR23). HRQoL was similar in the two treatment groups. Approximately 11% of patients in the combination arm and 10% in the monotherapy arm did not complete a quality of life questionnaire at least once either at baseline or during the treatment phase.
Table 15: Clinical Trial of Docetaxel In Combination With Capecitabine in the Treatment of Breast Cancer- Pivotal Study - Combination Therapy
| Design Diagnosis | Drug/Dosage | No. Women Enrolled | Results |
Open label, randomized, parallel group. Females with advanced and/or metastatic breast cancer resistant to or recurring during or after anthracycline containing therapy or relapsing during or recurring within 2 years of completing anthracycline-containing adjuvant therapy | Capecitabine 2500 mg/m2/day for 2 weeks with a 1 week rest period in combination with Docetaxel 75 mg/m2 every 3 weeks | 255 | Response Rate Combination therapy: 41.6% Docetaxel monotherapy: 29.7% (p=0.0058) Time to Disease Progression Combination therapy: 186 days Docetaxel monotherapy: 128 days (p=0.0001) Hazard Ratio: 0.643 Overall Survival Combination therapy: 442 days Docetaxel monotherapy: 352 days (p= 0.0126) Hazard Ratio: 0.775 |
| Docetaxel 100 mg/m2 every 3 weeks | 256 | ||
Non-Small Cell Lung Cancer
Monotherapy:
A) Six phase II studies were conducted in patients with locally advanced or metastatic non-small cell lung cancer. A total of 160 patients had received no prior chemotherapy (previously untreated), and 88 patients had received prior platinum-based therapy (previously treated), which included 37 patients who had progressive disease with platinum therapy (platinum refractory). In these clinical trials, docetaxel was administered at a 100 mg/m2 dose given as a one-hour infusion every 3 weeks.
B) Six additional phase II studies were conducted in 337 patients with naive locally advanced non-small cell lung cancer. In these clinical trials, docetaxel was administered at a 100 mg/m2 dose given as a one-hour infusion.
C) One phase III study was conducted in 137 patients with naive locally advanced non-small cell lung cancer. In this clinical trial, docetaxel was administered at a 100 mg/m2 dose given as a one-hour infusion every 3 weeks.
Combination Therapy:
D) Two phase II studies were conducted in 98 patients with naive locally advanced non-small cell lung cancer. In these clinical trials, two different schedules have been tested: docetaxel at 75 mg/m2 combined with cisplatin at 75 mg/m2 given as a one-hour infusion every 3 weeks; and docetaxel at 75 mg/m2 combined with cisplatin at 100 mg/m2 given as a one-hour infusion every 3 weeks for 3 cycles and then every 6 weeks.
E) One phase II study was conducted in 44 patients with naive locally advanced non-small cell lung cancer. In this clinical trial, docetaxel was administered at 100 mg/m2 on Day 1, alternating with cisplatin at 120 mg/m2 on Day 21, every 6 weeks, with a modified cisplatin dose to 100 mg/m2 from the third administration.
The overall response rates, median survival time, median duration of response and median time to progression are represented in the following table:
Table 16: Clinical Trials of Docetaxel in Non-Small Cell Lung Cancer
| Overall Response Rate | Median Survival Time | Median Duration of Response | Median Time to Progression | |||||||||
|---|---|---|---|---|---|---|---|---|---|---|---|---|
| Monotherapy | ||||||||||||
| A) Previously untreated patients (N=160) | 19% | 8 months | 29 weeks | 14 weeks | ||||||||
| A) Previously treated patients (N=88) | 31% | 9 months | 25 weeks | 14 weeks | ||||||||
| B) Previously untreated patients (N=337) | 20–31% | 8.5–10 months | 5.9 weeks | 2–3 months | ||||||||
| C) Previously untreated patients (N=137) | 18% | 6 months | 37 weeks | 13 weeks | ||||||||
| Combination therapy | ||||||||||||
| D) Previously untreated patients (N=98) | 36% | 9 months | 6 months | 4 months | ||||||||
| E) Previously untreated patients (N=44) | 36 % | 9 months | 10 months | 4 months | ||||||||
| Overall | 18–36% | 6–10 months | 6–10 months | 2–4 months | ||||||||
The adverse reaction profile from these naive locally advanced non-small cell lung cancer patients is similar to larger populations studied for metastatic breast cancer (see 8 ADVERSE REACTIONS).
Ovarian Cancer
Docetaxel was studied in five phase II clinical trials in patients who were diagnosed with advanced epithelial ovarian cancer and who failed a previous treatment with cisplatin and/or to carboplatin. These patients (n=281) received docetaxel 100mg/m2 every three weeks as a one-hour infusion.
The overall response rate was 26.7% with a 5.7% complete response rate. The median survival ranged from 11.2 to 11.9 months.
From the five clinical trials in patients with advanced epithelial ovarian cancer, the adverse reaction profile from these 281 patients is similar to larger populations studied for metastatic breast cancer (see 8 ADVERSE REACTIONS).
Prostate Cancer
The safety and efficacy of docetaxel in combination with prednisone or prednisolone in patients with androgen-independent (hormone refractory) metastatic prostate cancer were evaluated in a randomized multicentre Phase III trial. A total of 1006 patients with KPS ≥ 60 were randomized to the following treatment groups:
- Docetaxel 75 mg/m2 every 3 weeks for 10 cycles.
- Docetaxel 30 mg/m2 administered weekly for the first 5 weeks in a 6 week cycle for 5 cycles.
- Mitoxantrone 12 mg/m2 every 3 weeks for 10 cycles.
All 3 regimens were administered in combination with prednisone or prednisolone 5 mg twice daily, continuously. Patients who received docetaxel every three weeks demonstrated statistically significant longer overall survival compared to those treated with mitoxantrone. The increase in survival seen in the docetaxel weekly arm was not statistically significant compared to the mitoxantrone control arm. Efficacy endpoints for the docetaxel arms versus the control arm are summarized in the following table:
Table 17: Efficacy of Docetaxel in the Treatment of Patients with Androgen-Independent
(Hormone-Refractory) Metastatic Prostate Cancer (Intent-to-Treat Analysis)
| Endpoint | Docetaxel 75 mg/m2 every 3 weeks | Docetaxel 30 mg/m2 every week | Mitoxantrone 12 mg/m2 every 3 weeks | ||||||||||||
| Number of patients | 335 | 334 | 337 | ||||||||||||
| Median survival (months) | 18.9 | 17.4 | 16.5 | ||||||||||||
| 95% CI | (17.0-21.2) | (15.7-19.0) | (14.4-18.6) | ||||||||||||
| Hazard ratio | 0.761 | 0.912 | -- | ||||||||||||
| 95% CI | (0.619-0.936) | (0.747-1.113) | -- | ||||||||||||
| p-value†* | 0.0094 | 0.3624 | -- | ||||||||||||
| Number of patients | 291 | 282 | 300 | ||||||||||||
| PSA response rate (%) | 45.4 | 47.9 | 31.7 | ||||||||||||
| 95% CI | (39.5-51.3) | (41.9-53.9) | (26.4-37.3) | ||||||||||||
| p-value* | 0.0005 | <0.0001 | -- | ||||||||||||
Number of patients Pain response rate (%) 95% CI p-value* | 153 34.6 (27.1-42.7) 0.0107 | 154 31.2 (24.0-39.1) 0.0798 | 157 21.7 (15.5-28.9) -- | ||||||||||||
| Number of patients | 141 | 134 | 137 | ||||||||||||
| Tumor response rate (%) | 12.1 | 8.2 | 6.6 | ||||||||||||
| 95% CI | (7.2-18.6) | (4.2-14.2) | (3.0-12.1) | ||||||||||||
| p-value* | 0.1112 | 0.5853 | -- | ||||||||||||
†Stratified log rank test *Threshold for statistical significance=0.0175 | |||||||||||||||
No statistical differences were observed between treatment groups for Global Quality of Life.
Differences in efficacy were not identified between elderly patients and younger patients.
In patients treated with docetaxel every three weeks, the following TEAEs, regardless of relationship to docetaxel occurred at rates ≥ 10% higher in patients 65 years of age or greater compared to younger patients: anemia (71% vs. 59%), infection (37% vs. 24%), nail changes (34% vs. 23%), anorexia (21% vs. 10%), weight loss (15% vs. 5%) respectively.
Fatigue, all grades, was one of the most commonly reported TEAEs (regardless of relationship to docetaxel) in patients treated with docetaxel every three weeks, but grade 3-4 were experienced in only 1.6% of subjects < 65 years old, 6.3% in those ≥ 65 years, and 10.4% in those ≥ 75 years old. Similarly diarrhea, all grades, was also commonly reported, but the incidence of grade 3-4 diarrhea was much lower for each age category, 1.6%, 2.4% and 3.0% respectively. There was a similar pattern for the incidence of infection grade 3-4, in the three age categories the incidence was 4.0%, 6.7%, and 9.0%, respectively.
Squamous Cell Carcinoma of the Head and Neck
Three phase II studies were conducted in 96 patients with recurrent and/or metastatic squamous cell carcinoma of the head and neck. In these clinical trials docetaxel 100 mg/m2 was given as a one-hour infusion every 3 weeks.
The overall response rate (ORR) for evaluable patients was 24 to 45% with 0 to 14% of complete responses (CR). The median duration of response was 19 to 21 weeks for two studies. The mean time to progression was 11 weeks for one study.
From these clinical trials in patients with squamous cell carcinoma of the head and neck, the adverse reaction profile from these patients is similar to large population studied for metastatic breast cancer (see 8 ADVERSE REACTIONS). There were no life-threatening serious or unexpected adverse reactions reported in these trials.
15 MICROBIOLOGY
No microbiological information is required for this drug product.
16 NON-CLINICAL TOXICOLOGY
General Toxicology
Autonomic and Central Nervous Systems: In rats, single administration of 1, 3 or 10 mg/kg docetaxel did not markedly affect the central nervous system. The studies carried out only revealed moderate, inconsistent sedative effects, the intensity of which was not dose-related. Docetaxel did not show any anticonvulsant or analgesic properties. In mice, docetaxel administered at doses of 3, 10 or 30 mg/kg had no effect on the duration of hexobarbital-induced sleep. Docetaxel has no specific effects on the autonomic nervous system.
Cardiovascular System: The effects of docetaxel on the cardiovascular system were studied in conscious or anaesthetised rats, conscious rabbits and conscious or anaesthetised dogs. The main pharmacological effects observed after administration of single doses of the drug are hypotension, a decrease in vascular resistance and tachycardia. These effects, the intensity of which was not dose-related, were observed in conscious or anaesthetised dogs but not in rats and rabbits. In the dog, they were accompanied by clinical signs subsequent to histamine release. It has been clearly shown that these effects were attributable to polysorbate 80, the vehicle used to solubilize docetaxel.
Respiratory System: In the anaesthetised guinea pig, docetaxel administered at doses of 0.3, 1 or 3 mg/kg did not change bronchopulmonary resistance or compliance. At 3 mg/kg, the test substance induced a 41% decrease in respiratory rate which was comparable to that caused by the vehicle alone.
Immune System: As opposed to many anticancer drugs, docetaxel has only moderate immunosuppressive activity. Indeed, in vitro, although docetaxel inhibits the proliferation of T-cells and production of lymphokine (interleukin 2 and 3) from concanavalin A stimulated T-lymphocytes (IC50 = 10-7 M), it has little or no effect on macrophage activation and TNF generation. Furthermore, in vivo, docetaxel has a protective effect against Listeria monocytogenes infection and has no immunosuppressive activity towards Klebsiella pneumoniae septicemia when administered to mice at doses of 10 and 20 mg/kg.
Gastrointestinal and Genito-Urinary Systems: Docetaxel had no effect on intestinal transit in rats at doses of 1, 3 or 10 mg/kg. In mice, a 15% increase in transit (single dose of 50 mg/kg) or 23% decrease (20 mg/kg for 5 days) was not biologically significant.
In water-loaded rats, Docetaxel at doses of 1, 3 or 10 mg/kg did not produce any changes in urine output, pH or urinary excretion of Na+, K+, Cl and protein.
Toxicity studies are summarized in tables on the following pages.
Acute Toxicity
Table 18: Acute Toxicity
Species of Animal/ Strain | Number Animals/ Dose Group | Route and Period of Admin | Admin Dose or Treatment (mg/m2/day) | Results |
| Mouse/CD2F1 | 10M, 10F | i.v. | 0, 222, 285, 363 and 468 | LD10 between 285 and 468 mg/m2 HNLD = 222 mg/m2 Clinical signs included non-extension and/or paresis of hind limbs from 222 mg/m2 |
| Mouse/CD2F1 | 10M, 10F | i.v. | 0, 192, 285, 363 and 468 | Males: HNLD = 285 mg/m2 LD10 = 345 mg/m2; LD50 = 414 mg/m2; LD90 = 468 mg/m2 Females: HNLD between 192 and 285 mg/m2 Clinical signs included non-extension and/or paresis of hind limbs from 192 mg/m2 |
Species of Animal/ Strain | Number Animals/ Dose Group | Route and Period of Admin | Admin Dose or Treatment (mg/m2/day) | Results |
| Mouse/CD2F1 | 10M, 10F (Interim Sacrifice of 5/sex/group on day 4) | i.v. | 0, 30, 144, 285, 468 | HNLD = 285 mg/m2 No NOEL observed Toxic effects: neurotoxic signs (axonal and myelin degeneration of the sciatic nerves, accompanied by non-extension of the hind-limbs); testicular changes; lympho-hematopoietic changes (including leucopenia and cortical atrophy of the thymus); body weight loss(neurotoxic and testicular changes were not reversible after 28 days in 468 mg/m2) |
| Rat/SD | 10M, 10F (Interim Sacrifice of 5/sex/group on day 4) | i.v. | 0, 60, 120, 180 and 240 | HNLD = 60 mg/m2. No NOEL observed. Reversible Toxic Effects: Decreased body weights; leucopenia (lymphopenia/ neutropenia); anemia (erythrocyte count, hemoglobin concentration, hematocrit). Bone Marrow Hyperplasia: Tissue atrophy of multiple organs. Irreversible Toxic Effects: Acute pulmonary changes (accumulation of alveolar macrophages, fibrosis of alveolar septa) – all doses, Testicular atrophy - 60/120 mg/m2 |
Species of Animal/ Strain | Number Animals/ Dose Group | Route and Period of Admin | Admin Dose or Treatment (mg/m2/day) | Results |
| Dog/Beagle | 2M; 2F (Interim Sacrifice of 1/sex/group on day 8) | i.v. | 0, 15, 30, 70 and 140 | HNTD = 15 mg/m2; TDL = 15 mg/m2; TDH = 30 mg/m2; LD50 = 50 mg/m2 Transient Clinical Signs: Subdued behaviour; abnormal respiration; peripheral vasodilation including reddening of the pinnae, gums, and snout (treated and controls). Diarrhea, red feces, tremors and head shaking (treated animals). Toxic Effects: Body weights, food consumption; packed cell volume, hemoglobin conc., erythrocyte counts; platelets; leucopenia; intestinal epithelium necrosis (all segments of the intestines); At Lethal Doses: Myelosuppression in sternum and femur; atrophy of the lymphoid organs; impaired kidney function. Recovery was complete at 15 and 30 mg/m2 |
Subacute Toxicity
Table 19: Subacute Toxicity
Species of Animal/ Strain | Number Animals/ Dose Group | Route and Period of Administration | Admin. Dose or Treatment (mg/m2/day) | Results |
| Mouse/CD2F1 | 10M, 10F | i.v. daily for 5 days | 0, 45, 54, 64.8, 78, 93.6 and 112.5 | HNLD: 54 mg/m2/day LD10= 60.3 mg/m2/day LD50= 90.3 mg/m2/day LD90= 135.6 mg/m2/day Clinical Signs: lethargy, decreased motor activity, ataxia, hair loss, blanching, hunched posture, non-extension/paresis of the hind limbs; body weights (first 2 weeks); local irritation at injection site (second and third weeks of observation). |
Species of Animal/ Strain | Number Animals/ Dose Group | Route and Period of Administration | Admin. Dose or Treatment (mg/m2/day) | Results |
| Mouse/CD2F 1 | 10M, 10F | i.v. daily for 5 days | 0, 6, 30, 60 and 90 | Significant Observations:
6 mg/m2/day: Slight reduction in lymphocyte count |
Table 20: Subchronic and Chronic Toxicity
Species of Animal/ Strain | Number Animals/ Dose Group | Route and Period of Administration | Admin. Dose or Treatment (mg/m2/day) | Results |
|---|---|---|---|---|
| Rat/Sprague- Dawley | 10M, 10F | i.v. daily for 28- 31 days | 0, 0.3, 0.6 and 1.2 | NOEL: 0.3 mg/m2/day Toxic Effects (confined to 1.2 mg/m2): slight food consumption (week 4, females); slight RBC, WBC, thrombocytes; slight ALAT, ASAT, ALP; testis weights; mild, diffuse degeneration of the seminiferous tubules accompanied by moderate hyposperma- togenesis (1 male). |
Species of Animal/ Strain | Number Animals/ Dose Group | Route and Period of Administration | Admin. Dose or Treatment (mg/m2/day) | Results |
|---|---|---|---|---|
| Rat/Sprague-Dawley | 15M, 15F | i.v. single dose every 3 weeks for 6 weeks | 0, 15, 30 and 60 | Reversible Effects: Body weight and food consumption; Lympho-hematopoietic changes (including RBC, WBC, platelet and reticulocyte counts; bone marrow hypocellularity; thymic and lymph nodes atrophy at 60 mg/m2); abnormal mitosis/single cell necrosis in multiple organs. Effects not reversible after 28 days: Testicular changes characterized by degeneration of seminiferous tubular epithelium (60 mg/m2/day) |
| Rat/Sprague-Dawley | 15M, 15F | i.v. single dose every 3 weeks for 6 months | 0, 1.2, 6 and 30 (plus additional saline control) | NOEL 0.2 mg/kg Reversible lympho-hematopoietic changes as characterized above (thymic and lymph node atrophy not observed). Testicular effects (as above) had not recovered after the 1-month recovery period. |
| Dog (Beagle) | 2M, 2F | i.v. daily for 5 days | 0, 3, 6, and 15 | HNTD = 3; TDL = 6; LDIOO = 15 mg/m2; 15 mg/m2: Body Weight/Food consumption; peripheral vasodilation (both treated and controls); emesis, diarrhea, moulting; lympho- hematopoietic changes (including, RBC, WBC, hemoglobin, platelet counts; fibrinogen; bone marrow atrophy in femur/sternum; atrophy of lymph node and white pulp of the spleen; cortical and medullary necrosis of thymus; intestinal epithelium necrosis (all segments of intestines) at lethal doses. |
Species of Animal/ Strain | Number Animals/ Dose Group | Route and Period of Administration | Admin. Dose or Treatment (mg/m2/day) | Results |
|---|---|---|---|---|
| Dog (Beagle) | 2M, 2F | i.v. single dose every 3 wks. for 12 wks | 0, 7.5, 15 and 30 | HNTD= 7.5; TDL = 15; TDH = 30 mg/m2; body weight/food consumption (30 mg/m2); peripheral vasodilatation (treated/controls); blood in feces (15 and 30); slight to moderate leukocyte count (30 mg/m2) - reversible in 2 weeks |
| Dog (Beagle) | 5M, 5F | i.v. single dose every 3 wks. for 28 wks. | 0, 2, 7.5 and 30 | HNTD= 2; TDL= 7.5; TDH= 30 mg/m2 At 30 mg/m2: erythema; edema (all doses including controls) more prevalent in this dose after 3rd cycle; diarrhea; vomitus (containing blood); alopecia; body weight/food consumption; ECG changes; reversible leukocyte and platelet counts, RBC; ASAT, ALP; hypoplasia of bone marrow (30 mg/m2); gastrointestinal changes; single-cell necrosis of epididymis and exocrine pancreas (females) at 7.5 and 30; At high dose: "clear" cell changes of the Hepatocytes |
Carcinogenicity:
No long-term animal studies have been performed to evaluate the carcinogenic potential of Docetaxel.
Genotoxicity:
Docetaxel was evaluated in a battery of genotoxic assays in vitro and in vivo. Docetaxel was devoid of mutagenic activity in the bacterial reverse mutation test (Ames test) and in the hypoxanthine-guanine phosphoribosyltransferase (HGPRT) test in Chinese Hamster Ovary cells (CHO- K1). However, in the chromosome aberration test in CHO-K1 cells, docetaxel induced an increase in aneuploid cells but was found to be devoid of any clastogenic activity. In the in vivo micronucleus test, docetaxel induced an increase in the number of micronucleated polychromatic erythrocytes in bone marrow. The increase in the incidence of micronucleated, aneuploid and polyploidy cells may be related to the pharmacological activity of docetaxel which induces inhibition of microtubule depolymerization.
Table 21: Mutagenicity and Genotoxicity
| Test | Test System | Route (mode) and Period of Admin. | Treatment Concentration (g/plate) | Results |
| Gene Mutation | S. typhimurium (TA 1535; TA 1537; TA 1538; TA 98 and TA 100 | Direct method | 62.5 - 1000 | Negative |
(without/with metabolic activation) | 62.5 - 1000 | Negative | ||
| Gene Mutation | E. coli | Direct method | 62.5 - 1000 | Negative |
| (wp2uvra) | (without/with metabolic | 62.5 - 1000 | Negative | |
| activation) | ||||
| Chromosome | CHO-K1 cells | Direct method | 0.5 - 2.0 | Negative |
| aberration | (without/with metabolic | 0.1 - 1.0 | Negative | |
| activation) | ||||
| Micronucleus | CHO-K1 cells | Direct method | 0.15 - 1.2 | Increase in |
| (without/with metabolic | 0.15 - 1.2 | micronucleated Cells | ||
| activation) | ||||
| Phase Distribution | CHO-K1 cells | Direct method | 0.05 - 1.0 | Appearance of aneuploid cells |
| HPRT | CHO-K1 cells | Direct method | 0.005 - 5 | Negative |
| (without/with metabolic | 0.005 - 5 | Negative | ||
| activation) | ||||
| Micronucleus (Bone marrow) | Mouse | i.v. - 2 doses, 24 h apart | 0.195 -7.2 mg/kg | Positive |
Reproductive and Developmental Toxicology:
Table 22: Fertility and General Reproductive Performance
Species of Animal/ Strain | Number Animals/ Group | Route and Period of Administration | Admin. Dose of Treatment (mg/m2/day) | Results |
(Segment I) Rat/Sprague- Dawley | 25M, 25F (add. 18F controls and 12F treated for hematology evaluation) | i.v. Males: 61 to 70 days prior mating Females: 15 days prior to mating until day 7 of gestation | Males: 0, 0.3, 0.9 and 1.7 (1.8) Females: 0, 0.3, 0.9 and 1.8 (1.35) ( )=reduced dose | NOEL Males: 0.5 mg/m2; Females: <0.5 mg/m2 Repro. NOEL: Males: 0.15 mg/m2, Females 0.05 mg/m2 Development NOEL: 0.05 mg/m2 Paternal Toxicity: body weight and food consumption (mid- and high- dose); hematological changes. No histopathological changes in testis or epididymidis. Maternal Toxicity: body weight and food consumption; hematological changes. Reproductive Performance: slight prolonged cohabitation at high dose. |
Table 23: Teratology
Species of Animal/ Strain | Number Animals/ Group | Route and Period of Administration | Admin. Dose of Treatment (mg/m2/day) | Results |
(Segment II) Rat/Sprague- Dawley | ca. 20 mated females | i.v. days 6 to 17 of gestation | 0, 0.18, 0.6 and 1.8 | Maternal Toxicity: body weight gains and food consumption with intrauterine mortality; litter size. F1 Generation: fetal body weight; delay in fetal ossification; at high dose: delay in development (physical, functional, and behavioral); no effect on reproductive performance. No teratogenic effects at doses tested. |
(Segment II) Rat/Sprague- Dawley | ca. 20 mated females | i.v. days 6 to 18 of gestation | 0, 0.36, 1.2, 2.4, and 3.6 | Maternal Toxicity: 3.6 and 2.4 mg/m2, severe toxicity (mortality, abortion, body weight loss, RBC, WBC, and platelets) with no fetal evaluation due to mortality. At 1.2 mg/m2: body weight and food consumption; platelets. F1 Generation: fetal body weight (at 1.2 mg/m2); delay in fetal ossification (at 1.2 and slightly at 0.36 mg/m2) No teratogenic effects |
Table 24: Peri- and Post-Natal Toxicology
Species of Animal/Strain | Number Animals/ Group | Route and Period of Administration | Admin. Dose of Treatment (mg/m2/day) | Results |
(Segment III) Rat/Sprague- Dawley | 28-32 mated females | i.v. Gestation day 15 to day 21 post-partum | 0, 0.24, 0.6 and 1.5 | F0 Generation: Maternal toxicity at 1.5 mg/m2 (body weight gains and food consumption) F1 Generation: Slight delay in physical and functional development at 1.5 mg/m2 F2 Generation: No development changes observed |
17 SUPPORTING PRODUCT MONOGRAPHS
Product Monograph: Taxotere (docetaxel for injection), Sanofi Aventis., Date of revision June 15, 2020, Control Number 237181