


Product Monograph - Edurant
RECENT MAJOR LABEL CHANGES
None at the time of the most recent authorization
TABLE OF CONTENTS
Sections or subsections that are not applicable at the time of authorization are not listed.
RECENT MAJOR LABEL CHANGES ......................................................................................... 2
TABLE OF CONTENTS ............................................................................................................... 2
PART I: HEALTH PROFESSIONAL INFORMATION .................................................................. 4
1 INDICATIONS ................................................................................................................... 4
1.1 Pediatrics .......................................................................................................... 4
1.2 Geriatrics ........................................................................................................... 4
2 CONTRAINDICATIONS ................................................................................................... 4
4 DOSAGE AND ADMINISTRATION .................................................................................. 5
4.1 Dosing Considerations ...................................................................................... 5
4.2 Recommended Dose and Dosage Adjustment ................................................. 5
4.4 Administration ................................................................................................... 6
4.5 Missed Dose ..................................................................................................... 6
5 OVERDOSAGE ................................................................................................................ 6
6 DOSAGE FORMS, STRENGTHS, COMPOSITION AND PACKAGING ......................... 6
7 WARNINGS AND PRECAUTIONS .................................................................................. 7
7.1 Special Populations ......................................................................................... 10
7.1.1 Pregnant Women ................................................................................. 10
7.1.2 Breast-feeding ...................................................................................... 11
7.1.3 Pediatrics ............................................................................................. 11
7.1.4 Geriatrics .............................................................................................. 11
8 ADVERSE REACTIONS ................................................................................................. 11
8.1 Adverse Reaction Overview ............................................................................ 11
8.2 Clinical Trial Adverse Reactions ..................................................................... 12
8.2.1 Clinical Trial Adverse Reactions - Pediatrics ........................................ 13
8.3 Less Common Clinical Trial Adverse Reactions ............................................. 13
8.4 Abnormal Laboratory Findings: Hematologic, Clinical Chemistry and Other Quantitative Data ............................................................................................................ 14
8.5 Post-Market Adverse Reactions ...................................................................... 16
9 DRUG INTERACTIONS .................................................................................................. 16
9.2 Drug Interactions Overview ............................................................................. 16
9.4 Drug-Drug Interactions .................................................................................... 17
9.5 Drug-Food Interactions ................................................................................... 24
9.6 Drug-Herb Interactions .................................................................................... 24
9.7 Drug-Laboratory Test Interactions .................................................................. 24
10 CLINICAL PHARMACOLOGY ....................................................................................... 24
10.1 Mechanism of Action ....................................................................................... 24
10.2 Pharmacodynamics ......................................................................................... 25
10.3 Pharmacokinetics ............................................................................................ 25
11 STORAGE, STABILITY AND DISPOSAL ...................................................................... 28
12 SPECIAL HANDLING INSTRUCTIONS ......................................................................... 28
PART II: SCIENTIFIC INFORMATION ....................................................................................... 29
13 PHARMACEUTICAL INFORMATION ............................................................................ 29
14 CLINICAL TRIALS ......................................................................................................... 29
14.1 Clinical Trials by Indication .............................................................................. 29
Treatment-Naïve Adult Patients ........................................................... 29
Treatment-Naïve Pediatric Patients (12 years to less than 18 years of age) ...................................................................................................... 34
15 MICROBIOLOGY ............................................................................................................ 34
16 NON-CLINICAL TOXICOLOGY ..................................................................................... 36
PATIENT MEDICATION INFORMATION .................................................................................. 38
PART I: HEALTH PROFESSIONAL INFORMATION
1 INDICATIONS
EDURANT® (rilpivirine), in combination with other antiretroviral agents, is indicated for the treatment of human immunodeficiency virus type 1 (HIV-1) infection in antiretroviral treatment-naïve adult and pediatric patients 12 years of age and older (and weighing ≥35 kg) with HIV-1 RNA less than or equal to 100,000 copies/mL at the start of therapy.
1.1 Pediatrics
Pediatrics (12 to <18 years of age and weighing at least 35 kg): The safety, efficacy and pharmacokinetics of Edurant has been established in antiretroviral treatment-naïve, HIV-1 infected pediatric subjects 12 to less than 18 years of age and weighing at least 35 kg (see 4.2 Recommended Dose and Dosage Adjustment, 10.3 Pharmacokinetics, Pediatrics and 14.1 Clinical Trials by Indication, Treatment-Naïve Pediatric Patients (12 years to less than 18 years of age)).
Pediatrics (<12 years of age): Edurant is not recommended for patients less than 12 years of age (see 7.1.3 Pediatrics).
1.2 Geriatrics
Geriatrics (>65 years of age): Clinical studies of Edurant did not include sufficient numbers of subjects aged 65 and over to determine whether they respond differently from adult subjects <65 years of age. Edurant should be used with caution in this population (see 7.1.4 Geriatrics, 4.2 Recommended Dose and Dosage Adjustment and 10.3 Pharmacokinetics, Geriatrics).
2 CONTRAINDICATIONS
- Edurant is contraindicated in patients who are hypersensitive to rilpivirine or to any ingredient in the formulation. For a complete listing of ingredients, see 6 DOSAGE FORMS, STRENGTHS, COMPOSITION AND PACKAGING.
- Co-administration of Edurant is contraindicated with drugs which induce CYP3A enzymes or increase gastric pH as this may result in significant decreases in the plasma concentrations of rilpivirine, a loss of virologic response and possible resistance to Edurant and to the NNRTI class of antiretrovirals. These drugs are listed in Table 1 (see 9 DRUG INTERACTIONS).
Table 1: Drugs that are contraindicated with Edurant
| Drug Class | Drugs within class that are contraindicated with Edurant |
| Anticonvulsants | carbamazepine, oxcarbazepine, phenobarbital, phenytoin |
| Antimycobacterials | rifapentine, rifampin |
| Glucocorticoids | systemic dexamethasone (more than a single dose) |
| Herbal products | St. John’s wort (Hypericum perforatum) |
| Proton pump inhibitors | esomeprazole, lansoprazole, omeprazole, pantoprazole, rabeprazole |
4 DOSAGE AND ADMINISTRATION
4.1 Dosing Considerations
- Viral load must be determined prior to initiation of therapy. Therapy must not be initiated in patients with a viral load ≥100,000 copies/mL.
- Edurant must always be given in combination with other antiretroviral medicinal products.
- Edurant must always be given with a meal.
4.2 Recommended Dose and Dosage Adjustment
Adults
The recommended dose of Edurant is one 25 mg tablet once daily which must be taken with a meal (see 10.3 Pharmacokinetics).
Geriatric Patients
Clinical studies of Edurant did not include sufficient numbers of subjects aged 65 and over to determine whether they respond differently from adult subjects <65 years of age. Edurant should be used with caution in this population (see 1.2 Geriatrics, 7.1.4 Geriatrics and 10.3 Pharmacokinetics, Geriatrics)
Pediatric Patients
Pediatric (12 to <18 years of age and weighing ≥35 kg)
The recommended dose of Edurant for pediatric patients 12 years to <18 years of age and weighing at least 35 kg is one 25 mg tablet once daily which must be taken with a meal (see 10.3 Pharmacokinetics, Pediatrics).
Pediatric (less than 12 years of age or <35 kg)
The safety and efficacy of Edurant in children less than 12 years of age or weighing <35 kg has not been established. (see 1.1 Pediatrics, 7.1.3 Pediatrics and 10.3 Pharmacokinetics, Pediatrics).
Pregnancy and Postpartum
The recommended dose of Edurant in pregnant patients is one 25 mg tablet once daily taken with a meal. Lower exposures of rilpivirine were observed during the 2nd and 3rd trimesters of pregnancy, therefore viral load should be monitored closely (see 7.1.1 Pregnant Women and 10.3 Pharmacokinetics, Pregnancy and Breast-feeding).
Hepatic Impairment
Edurant has not been studied in patients with severe hepatic impairment (Child-Pugh score C) and the use of Edurant is not recommended in this population. No dose adjustment of Edurant is required in patients with mild (Child-Pugh Class A) or moderate (Child-Pugh Class B) hepatic impairment. However, given that the metabolism of Edurant is cytochrome P450-mediated and that clinical experience in patients with mild or moderate hepatic impairment is limited, caution should be exercised when administering Edurant to this population (see 7 WARNINGS AND PRECAUTIONS, Hepatic Impairment and 10.3 Pharmacokinetics, Hepatic Insufficiency).
Renal Impairment
Edurant has not been studied in patients with renal impairment. Caution should be exercised when administering Edurant to patients with severe renal impairment or end-stage renal disease whose drug absorption, distribution and metabolism may be altered secondary to renal dysfunction. No dose adjustment of Edurant is required in patients with mild to moderate renal impairment. As 99.7% of rilpivirine is bound to plasma proteins, it is unlikely that it will be significantly removed by hemodialysis or peritoneal dialysis (see 7 WARNINGS AND PRECAUTIONS, Renal and 10.3 Pharmacokinetics, Renal Insufficiency).
Dose adjustment with Rifabutin coadministration
For patients concomitantly receiving rifabutin, the Edurant dose should be increased to 50 mg (two tablets of 25 mg each) once daily, taken with a meal. When rifabutin co-administration is stopped, the Edurant dose should be decreased to 25 mg once daily, taken with a meal (see 9.4 Drug-Drug Interactions).
4.4 Administration
- Edurant tablets should be swallowed whole with water.
- Edurant must be taken with a meal.
4.5 Missed Dose
If the patient misses a dose of Edurant within 12 hours of the time it is usually taken, the patient should take Edurant with a meal as soon as possible, and then take the next dose of Edurant at the regularly scheduled time.
If a patient misses a dose of Edurant by more than 12 hours, the patient should not take the missed dose, but resume the usual dosing schedule.
5 OVERDOSAGE
There is no specific antidote for overdose with Edurant. Human experience of overdose with Edurant is limited. Treatment of overdose with Edurant consists of general supportive measures including monitoring of vital signs and ECG (QT interval) as well as observation of the clinical status of the patient. Since rilpivirine is highly protein bound to plasma protein, dialysis is unlikely to result in significant removal of the active substance.
| For management of a suspected drug overdose, contact your regional poison control centre. |
|---|
6 DOSAGE FORMS, STRENGTHS, COMPOSITION AND PACKAGING
| Route of Administration | Dosage Form / Strength / Composition | Non-medicinal Ingredients |
|---|---|---|
| Oral | Tablet, 25 mg | croscarmellose sodium, hypromellose 2910 6 mPa.s, lactose monohydrate, magnesium stearate, polyethylene glycol 3000, polysorbate 20, povidone K30, silicified microcrystalline cellulose, titanium dioxide and triacetin. |
Edurant tablets are supplied as white to off-white, film-coated, round, biconvex, tablets for oral administration containing rilpivirine hydrochloride equivalent to 25 mg of rilpivirine.
Each tablet is debossed with “TMC” on one side and “25” on the other side. Edurant tablets are packaged in high-density polyethylene (HDPE) bottles in the following configuration: 25 mg tablets - bottles of 30.
7 WARNINGS AND PRECAUTIONS
General
Transmission of HIV
Patients should be advised that current antiretroviral therapy does not cure HIV. Appropriate precautions to prevent the transmission of HIV should continue to be employed.
Virologic failure and development of resistance
In the pooled analysis from the Phase III trials, more Edurant-treated subjects with baseline HIV-1 RNA >100,000 copies/mL experienced virologic failure compared to subjects with HIV-1 RNA ≤100,000 copies/mL at baseline (see 7 WARNINGS AND PRECAUTIONS, Sensitivity/Resistance, and 15 MICROBIOLOGY, Resistance and Cross-resistance).
Regardless of HIV-1 RNA at the start of therapy, more Edurant-treated subjects with CD4+ cell count less than 200 cells/mm3 at the start of therapy experienced virologic failure compared to subjects with CD4+ cell count greater than or equal to 200 cells/mm3 (see 14 CLINICAL TRIALS).
The observed virologic failure rate in Edurant-treated subjects conferred a higher rate of overall treatment resistance and cross-resistance to the NNRTI class compared to the control (efavirenz) (see 7 WARNINGS AND PRECAUTIONS, Sensitivity/Resistance, and 15 MICROBIOLOGY, Resistance and Cross-resistance).
More subjects treated with Edurant developed tenofovir and lamivudine/emtricitabine associated resistance compared to the control (see 7 WARNINGS AND PRECAUTIONS, Sensitivity/Resistance and 15 MICROBIOLOGY, Resistance, Cross-resistance).
Interactions with medicinal products
Caution should be exercised when prescribing Edurant (rilpivirine) with drugs that may reduce the exposure of rilpivirine (see 2 CONTRAINDICATIONS and 9 DRUG INTERACTIONS).
As with other antiretroviral medicinal products, resistance testing should guide the use of Edurant (see 15 MICROBIOLOGY).
Carcinogenesis and Mutagenesis
Rilpivirine induced benign and malignant tumors in the liver of mice and rats. These tumors are caused by the enzyme induction that rilpivirine caused in these species which may be rodent-specific. In rats rilpivirine caused benign and malignant tumors of the thyroid follicular cells. These tumors are the result of continuous stimulation of the follicular cells due to the increased clearance of thyroxine caused by rilpivirine in this species. This effect is considered rat specific.
Cardiovascular
Edurant should be administered with caution to patients who are suspected to be at an increased risk of experiencing proarrhythmic conditions such as hypokalemia, clinically significant bradycardia, acute myocardial ischemia, congestive heart failure or congenital prolongation of QTc interval (see 8.4 Abnormal Laboratory Findings: Hematologic, Clinical Chemistry and Other Quantitative Data, Electrocardiogram Findings, 9.4 Drug-Drug Interactions, QT Prolonging Drugs and 10.2 Pharmacodynamics).
In healthy subjects, rilpivirine has been associated with prolongation of the QT interval of the electrocardiogram at doses of 75 mg and 300 mg once daily. In antiretroviral naïve, HIV-1 infected patients receiving Edurant 25 mg once daily in Phase III clinical trials, which excluded subjects with high risk factors for proarrhythmia, the mean QTc interval increased gradually over 48 weeks and remained stable through Week 96. An increase of >60 ms in QTcF interval resulting in abnormal values of >480 ms was reported in one patient. Prolongation of QT interval may increase the risk of cardiac arrhythmias.
There is limited information available on the potential for a pharmacodynamic interaction between Edurant and drugs that prolong the QTc interval of the electrocardiogram.
Edurant should be used with caution when co-administered with drugs with a known risk of Torsade de Pointes.
Endocrine and Metabolism
Serum Lipids and Blood Glucose
Serum lipids and blood glucose may increase during antiretroviral therapy. Disease control and lifestyle changes may also be contributing factors. Consideration should be given to the measurement of serum lipids and blood glucose. Lipid disorders and blood glucose elevations should be managed as clinically appropriate.
Gastrointestinal
Edurant contains lactose. This medicine is not recommended for patients with rare hereditary problems of galactose intolerance (severe lactase deficiency or glucose-galactose malabsorption).
Hepatic/Biliary/Pancreatic
Hepatotoxicity
Hepatic adverse events have been reported in patients receiving a rilpivirine containing regimen. Patients with underlying hepatitis B or C or marked elevations in transaminases prior to treatment may be at increased risk for worsening or development of transaminase elevations with use of Edurant. A few cases of hepatic toxicity have been reported in patients receiving a rilpivirine-containing regimen who had no pre-existing hepatic disease or other identifiable risk factors. Appropriate laboratory testing prior to initiating therapy and monitoring for hepatotoxicity during therapy with Edurant is recommended in patients with underlying hepatic disease such as hepatitis B or C, or in patients with marked elevations in transaminases prior to treatment initiation. Liver enzyme monitoring should also be considered for patients without pre-existing hepatic dysfunction or other risk factors.
Hepatic Impairment
Edurant has not been studied in patients with severe hepatic impairment (Child-Pugh score C) and the use of Edurant is not recommended in this population. No dose adjustment of Edurant is required in patients with mild (Child-Pugh Class A) or moderate (Child-Pugh Class B) hepatic impairment. However, given that the metabolism of Edurant is cytochrome P450-mediated and that clinical experience in patients with mild or moderate hepatic impairment is limited, caution should be exercised when administering Edurant to this population (see 4.2 Recommended Dosage and Dosage Adjustment, Hepatic Impairment and 10.3 Pharmacokinetics, Hepatic Insufficiency).
Immune
Immune Reconstitution Inflammatory Syndrome
Immune reconstitution inflammatory syndrome has been reported in patients treated with combination antiretroviral therapy, including Edurant. During the initial phase of treatment, patients responding to antiretroviral therapy may develop an inflammatory response to indolent or residual opportunistic infections (such as MAC, CMV, PCP and TB), which may necessitate further evaluation and treatment.
Autoimmune disorders (such as Graves’ disease, autoimmune hepatitis, polymyositis and Guillain-Barré syndrome) have also been reported to occur in the setting of immune reconstitution, however, the time to onset is more variable, and can occur many months after initiation of treatment. Sometimes there can be an atypical presentation.
Psychiatric
Depressive Disorders
During the Phase III trials (N=686), the incidence of depressive disorder adverse drug reactions (depressed mood, depression, dysphoria, major depression, mood altered, negative thoughts, suicide attempt, suicidal ideation) of at least moderate intensity (Grades 2 to 4) was 5%. The incidence of discontinuation due to depressive disorders was 1%. Suicide attempt was reported in 2 subjects while suicide ideation was reported in 4 subjects taking in Edurant. Patients with severe depressive symptoms should seek immediate medical evaluation to assess the possibility that the symptoms are related to Edurant, and if so, to determine whether the risks of continued therapy outweigh the benefits. The incidence of these events was similar in the control (efavirenz) group.
During the Phase II trial in pediatric subjects 12 to less than 18 years of age (N = 36) receiving Edurant through 48 weeks, the incidence of depressive disorders (regardless of causality, severity) was 19.4% (7/36). Most events were mild or moderate in severity. The incidence of Grade 3 and 4 depressive disorders (regardless of causality) was 5.6% (2/36). None of the subjects discontinued due to depressive disorders. Suicidal ideation and suicide attempt were reported in 1 subject.
Renal
Renal Impairment
Edurant has not been studied in patients with renal impairment. Caution should be exercised when administering Edurant to patients with severe renal impairment or end-stage renal disease whose drug absorption, distribution and metabolism may be altered secondary to renal dysfunction. No dose adjustments are required in patients with mild to moderate renal impairment. As 99.7% of rilpivirine is bound to plasma proteins, it is unlikely that it will be significantly removed by hemodialysis or peritoneal dialysis (see 4.2 Recommended Dose and Dosage Adjustment, Renal Impairment and 10.3 Pharmacokinetics, Renal Insufficiency).
Sensitivity/Resistance
Resistance/Cross-resistance
In the pooled analysis from two Phase III trials in adults, the emergence of resistance among subjects was greater in the Edurant arm as compared to the control (efavirenz) arm at Week 48 (10.6%, 5.3%, respectively) and at Week 96 (14%, 7.6%, respectively). More Edurant-treated subjects with baseline HIV-1 RNA >100,000 copies/mL experienced virologic failure compared to subjects with HIV-1 RNA ≤100,000 copies/mL at baseline.
The observed virologic failures in Edurant-treated subjects conferred a higher cross-resistance to the NNRTI class as compared to those in control-treated subjects. More subjects treated with Edurant developed lamivudine/emtricitabine associated resistance as compared to those treated with the control (see 15 MICROBIOLOGY, Resistance and Cross-resistance).
In the 36 adolescents 12 to less 18 years of age, treatment-emergent rilpivirine resistance mutations were detected in 5/8 (62.5%) subjects with virologic failure, treatment-emergent NNRTI resistance mutations were detected in 6 (75%) subjects. In 4/5 subjects, treatment emergent NRTI resistance was also detected. The observed treatment-emergent rilpivirine, NNRTI and NRTI resistance mutations were previously identified in adults (see 15 MICROBIOLOGY, Resistance and Cross-resistance).
In study C213, phenotypic resistance to NRTIs and phenotypic cross-resistance between rilpivirine and other NNRTIs was shown for efavirenz, nevirapine, and etravirine in 4/5 (80%) subjects with rilpivirine associated mutations.
Skin
Severe skin and hypersensitivity reactions have been reported during the post-marketing experience, including cases of Drug Reaction with Eosinophilia and Systemic Symptoms (DRESS), with rilpivirine-containing regimens. While some skin reactions were accompanied by constitutional symptoms such as fever, other skin reactions were associated with organ dysfunctions, including elevations in hepatic serum biochemistries. During the Phase III clinical trials, treatment-related rashes with at least Grade 2 severity were reported in 3% of subjects receiving Edurant. No grade 4 rash was reported. Overall, most rashes were Grade 1 or 2 and occurred in the first four to six weeks of therapy (see 8 ADVERSE REACTIONS). Discontinue Edurant immediately if signs or symptoms of severe skin or hypersensitivity reactions develop, including but not limited to, severe rash or rash accompanied by fever, blisters, mucosal involvement, conjunctivitis, facial edema, angioedema, hepatitis or eosinophilia. Clinical status including laboratory parameters should be monitored and appropriate therapy should be initiated.
7.1 Special Populations
7.1.1 Pregnant Women
No well-controlled clinical or pharmacokinetic studies of Edurant use in pregnant women have been conducted. Studies in animals have shown no evidence of relevant embryonic or fetal toxicity or an effect on reproductive function (see 16 NON-CLINICAL TOXICOLOGY, Reproductive and Developmental Toxicity).
There was no teratogenicity with rilpivirine in rats and rabbits. The exposures at the embryo-fetal No Observed Adverse Effects Levels (NOAELs) in rats and rabbits were respectively 15 and 70 times higher than the exposure in humans at the recommended therapeutic dose (see 16 NON-CLINICAL TOXICOLOGY; Reproductive and Developmental Toxicity). Edurant should not be used during pregnancy unless the potential benefits outweigh the potential risks.
Antiretroviral Pregnancy Registry
To monitor maternal-fetal outcomes of pregnant women exposed to Edurant, an Antiretroviral Pregnancy Registry has been established. Physicians are encouraged to register patients by calling 1-800-258-4263.
Rilpivirine in combination with a background regimen was evaluated in a clinical trial of 19 pregnant women during the second and third trimesters, and postpartum. The pharmacokinetic data demonstrate that total exposure (AUC) to rilpivirine as a part of an antiretroviral regimen was approximately 30% lower during pregnancy compared with postpartum (6-12 weeks). Virologic response was preserved throughout the trial period. No mother to child transmission occurred in all 10 infants born to the mothers who completed the trial and for whom the HIV status was available. Rilpivirine was well tolerated during pregnancy and postpartum. There were no new safety findings compared with the known safety profile of rilpivirine in HIV-1 infected adults. (10.3 Pharmacokinetics, Pregnancy and Breast-feeding).
7.1.2 Breast-feeding
It is not known whether rilpivirine is secreted in human milk. Because of both the potential for HIV transmission and the potential for adverse reactions in nursing infants, mothers should be instructed not to breast-feed if they are receiving Edurant (see 16 NON-CLINICAL TOXICOLOGY; Reproductive and Developmental Toxicity).
7.1.3 Pediatrics
Pediatrics (<12 years of age): Safety and effectiveness in pediatric patients less than 12 years of age has not been established.
7.1.4 Geriatrics
Geriatrics (>65 years of age): Clinical studies of Edurant did not include sufficient numbers of subjects aged 65 and over to determine whether they respond differently from adult subjects <65 years of age. Edurant should be used with caution in this population.
8 ADVERSE REACTIONS
8.1 Adverse Reaction Overview
The safety assessment of Edurant at Week 48 and Week 96 is based on pooled data from 686 patients in the Phase III controlled trials TMC278-C209 (ECHO) and TMC278-C215 (THRIVE) in antiretroviral treatment-naïve HIV-1 infected adult patients who received Edurant (25 mg once daily) (see 14 CLINICAL TRIALS). In the Week 96 analysis, the median duration of exposure was 104.3 weeks. The proportion of subjects who discontinued treatment with Edurant due to adverse drug reactions (ADRs) was 1.7%. The most frequently reported ADRs (≥2%) that were at least Grade 2 in severity were depression (4.1%), insomnia (3.5%), headache (3.5%), rash (2.3%), and abdominal pain (2.0%) (see Table 2). Most ADRs occurred during the first 48 weeks of treatment and no new ADR terms were identified between 48 weeks and 96 weeks (Phase III trials TMC278-C209 and TMC278-C215) and in the Phase IIb trial (TMC278-C204) through 240 weeks.
8.2 Clinical Trial Adverse Reactions
Clinical trials are conducted under very specific conditions. The adverse reaction rates observed in the clinical trials; therefore, may not reflect the rates observed in practice and should not be compared to the rates in the clinical trials of another drug. Adverse reaction information from clinical trials may be useful in identifying and approximating rates of adverse drug reactions in real-world use.
Clinical ADRs of at least moderate intensity or greater (≥Grade 2) reported in adult subjects treated with Edurant are presented in Table 2.
Table 2: Treatment-Emergent Adverse Drug Reactions1 of at Least Moderate Intensity2 (Grades 2-4) in ≥1% of Antiretroviral Treatment-Naïve, HIV-1-Infected Adult Subjects Treated with Edurant
System Organ Class, Preferred Term | Pooled Data from the TMC278-C209 (ECHO) and TMC278 C215 (THRIVE) Trials (Week 96 Analysis) | |||||
|---|---|---|---|---|---|---|
Edurant + BR N=686 | Efavirenz + BR N=682 | |||||
| Gastrointestinal Disorders | ||||||
| Abdominal Pain | 14 (2.0%) | 13 (1.9%) | ||||
| Nausea3 | 9 (1.3%) | 19 (2.8%) | ||||
| Vomiting | 7 (1.0%) | 14 (2.1%) | ||||
| Diarrhea | 7 (1.0%) | 9 (1.3%) | ||||
General Disorders and Administration Site Conditions | ||||||
| Fatigue | 11 (1.6%) | 14 (2.1%) | ||||
| Metabolism and Nutrition Disorders | ||||||
| Decreased Appetite | 8 (1.2%) | 4 (0.6%) | ||||
| Nervous System Disorders | ||||||
| Headache3 | 24 (3.5%) | 26 (3.8%) | ||||
| Dizziness3,5 | 7 (1.0%) | 46 (6.7%) | ||||
| Psychiatric Disorders | ||||||
| Depression | 28 (4.1%) | 22 (3.2%) | ||||
| Insomnia | 24 (3.5%) | 24 (3.5%) | ||||
| Abnormal Dreams3,4 | 11 (1.6%) | 27 (4.0%) | ||||
| Sleep Disorders | 9 (1.3%) | 6 (0.9%) | ||||
| Skin and Subcutaneous Tissue Disorders | ||||||
| Rash3,5 | 16 (2.3%) | 65 (9.5%) | ||||
N = total number of subjects per treatment group; BR = background regimen
- 1. Includes adverse reactions at least possibly, probably, or very likely related to the drug.
- 2. Intensities are defined as follows: Moderate (discomfort enough to cause interference with usual activity); Severe (incapacitating with inability to work or do usual activity).
- 3. Treatment comparison was pre-specified for these ADRs (Fisher’s Exact Test)
- 4. p-value <0.01
- 5. p-value <0.0001
8.2.1 Clinical Trial Adverse Reactions - Pediatrics
Adverse Drug Reactions from a Clinical Trial in Pediatric Patients (12 to less than 18 Years of Age and Weighing at Least 35 kg)
The safety assessment is based on the Week 48 analysis of the single-arm, open-label, Phase II trial, TMC278-C213, in which 36 antiretroviral treatment-naïve HIV-1 infected patients 12 to less than 18 years of age and weighing at least 35 kg received Edurant (25 mg once daily) in combination with other antiretroviral agents (see 14 CLINICAL TRIALS). The median duration of exposure was 63.5 weeks. There were no patients who discontinued treatment due to ADRs. No new ADRs were identified compared to those seen in adults.
ADRs were reported in nineteen pediatric subjects (52.8%). Most ADRs were Grade 1 or 2. The most common ADRs (all grades, in at least two subjects) were headache (19.4%), depression (19.4%), somnolence (13.9%), and nausea (11.1%), dizziness (8.3%), abdominal pain (8.3%), vomiting (5.6%) and rash (5.6%). Observed laboratory abnormalities were comparable to those in adults.
Adrenal Function
In trial TMC278-C213, at Week 48, the overall mean change from baseline in basal cortisol showed an increase of 1.59 (0.24, 2.93) micrograms/dL.
Six of 30 (20%) subjects with a normal 250 micrograms ACTH stimulation test at baseline developed an abnormal 250 micrograms ACTH stimulation test (peak cortisol level <18.1 micrograms/dL) during the trial. Three of these subjects had an abnormal 250 micrograms ACTH stimulation test at Week 48. Overall, there were no serious adverse events, deaths, or treatment discontinuations that could clearly be attributed to adrenal insufficiency. The clinical significance of the abnormal 250 micrograms ACTH stimulation tests is not known.
8.3 Less Common Clinical Trial Adverse Reactions
Treatment-emergent ADRs of at least moderate intensity (≥ Grade 2) occurring in less than 1% of antiretroviral treatment-naïve subjects receiving Edurant are listed below by System Organ Class. Some adverse events (*) have been included because of investigator’s assessment of potential causal relationship and were considered serious or have been reported in more than 1 subject treated with Edurant.
Gastrointestinal Disorders: abdominal discomfort
Hepatobiliary Disorders: cholecystitis*, cholelithiasis*
Nervous System Disorders: somnolence
Psychiatric Disorders: anxiety, depressed mood
Renal and Urinary Disorders: glomerulonephritis membranous*, glomerulonephritis mesangioproliferative*, nephrolithiasis*
8.4 Abnormal Laboratory Findings: Hematologic, Clinical Chemistry and Other Quantitative Data
Selected treatment-emergent clinical laboratory abnormalities (Grade 3 or Grade 4) reported in Edurant-treated subjects are shown in Table 3.
Table 3: Selected Treatment Emergent Laboratory Abnormalities (Grade 3 or Grade 4) Observed in Antiretroviral Treatment-Naïve, HIV-1 Infected Adult Patients (Week 96 Analysis)
| Laboratory Parameter Abnormality | DAIDS Toxicity Range | Pooled Data from the TMC278-C209 (ECHO) and TMC278-C215 (THRIVE) Trials | |
|---|---|---|---|
Edurant + BR N=686 | Efavirenz + BR N=682 | ||
| HEMATOLOGY | |||
| Decreased hemoglobin | < 4.5 mmol/L < 7.4 g/dl | 0.1% | 0.6% |
| Decreased platelet count | < 49999/mm3 < 49999 x 109/L | 0.1% | 0.3% |
| Decreased white blood cell count | < 1499/mm3 < 1.499 giga/L | 1.2% | 1.0% |
| BIOCHEMISTRY | |||
| Increased creatinine | > 1.8 x ULN | 0.1% | 0.1% |
| Increased AST | > 5.0 x ULN | 2.3% | 3.3% |
| Increased ALT | > 5.0 x ULN | 1.6% | 3.7% |
| Increased bilirubin | > 2.5 x ULN | 0.7% | 0.3% |
| Increased pancreatic amylase | > 2 x ULN | 3.8% | 4.8% |
| Increased lipase | > 3 x ULN | 0.9% | 1.6% |
| Increased total cholesterol (fasted)1 | > 7.77 mmol/L > 300 mg/dL | 0.1% | 3.3% |
| Increased LDL cholesterol (fasted)1 | ≥ 4.91 mmol/L ≥ 191 mg/dL | 1.5% | 5.3% |
| Increased Triglycerides (fasted)1 | ≥ 8.49 mmol/L ≥ 751 mg/dL | 0.6% | 3.3% |
BR = background regimen; ULN=upper limit of normal N = number of subjects per treatment group
- 1. p ≤0.001 according to Fisher’s Exact test (difference in grade 3 plus 4 abnormalities between the two treatment groups).
Note: Percentages were calculated for the number of subjects with results for the analyte.
Adrenal Function
In the pooled analysis of Phase III trials, at Week 48, the overall mean change from baseline in basal cortisol showed a decrease of 13.1 nmol/L in the Edurant group and an increase of 9.0 nmol/L in the efavirenz (control) group. At Week 96, the overall mean change from baseline in basal cortisol showed a decrease of 19.1 nmol/L in the Edurant group and a decrease of 0.6 nmol/L in the efavirenz group. At Week 48 and Week 96, the mean change from baseline in ACTH-stimulated cortisol levels was lower in the Edurant group (+16.5 ± 6.14 nmol/L and +18.4 ± 8.36 nmol/L, respectively) than in the efavirenz group (+58.1 ± 6.66 nmol/L and +54.1 ± 7.24 nmol/L, respectively). Mean values for both basal and ACTH-stimulated cortisol values at Week 48 and Week 96 were within the normal range. Overall, there were no serious adverse events, deaths, or treatment discontinuations that could clearly be attributed to adrenal insufficiency.
Serum Creatinine
In the pooled Phase III trials, an increase in serum creatinine was observed over the 96 weeks of treatment with Edurant. Most of this increase occurred within the first four weeks of treatment, with a mean change of 0.1 mg/dL (range: -0.3 mg/dL to 0.6 mg/dL) observed after 96 weeks of treatment. In subjects who entered the trial with mild or moderate renal impairment, the serum creatinine increase observed was similar to that seen in subjects with normal renal function. These changes are not considered to be clinically relevant and no subject discontinued treatment due to increases in serum creatinine. Serum creatinine increases occurred regardless of the background N(t)RTI regimen.
Serum Lipids
Changes from baseline in total cholesterol, LDL-cholesterol, HDL-cholesterol and triglycerides are presented in Table 4. The mean changes from baseline were smaller in the Edurant arm versus the comparator (efavirenz) arm. The impact of such findings has not been demonstrated.
Table 4: Treatment-Emergent Changes in Serum Lipids from Baseline to Week 96 in Treatment-Naïve HIV-1 Infected Adult Patients1 (Fasting); Data Pooled from the Phase III Trials, TMC278-C209 (ECHO) and TMC278-C215 (THRIVE)
| Lipid Parameters | Edurant + BR2 N3=686 | Efavirenz + BR N3=682 | ||||||||||||||
|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|
| n4 | Baseline | Week 96 | n4 | Baseline | Week 96 | |||||||||||
Mean (mg/dL) | Mean (mg/dL) | Mean change5 (mg/dL) | Mean (mg/dL) | Mean (mg/dL) | Mean change5 (mg/dL) | |||||||||||
| Total cholesterol6 | 546 | 161 | 166 | 5 | 507 | 160 | 187 | 28 | ||||||||
| HDL-cholesterol6 | 545 | 41 | 46 | 4 | 505 | 40 | 51 | 11 | ||||||||
| LDL-cholesterol6 | 543 | 96 | 98 | 1 | 503 | 95 | 109 | 14 | ||||||||
| Triglycerides6 | 546 | 122 | 116 | -6 | 507 | 130 | 141 | 11 | ||||||||
- 1. Excludes subjects who received lipid lowering agents during the treatment period.
- 2. BR, Background regimen.
- 3. N, Number of patients in the treatment groups.
- 4. n, Number of patients with both baseline and Week 96 values.
- 5. The change from baseline is the mean of within patient changes from baseline for patients with both baseline and Week 96 values.
- 6. p-value <0.001, Wilcoxon rank-sum test for treatment comparison (Edurant + BR versus Efavirenz + BR) of change from baseline.
HDL, High Density Lipoprotein. HDL-Cholesterol, cholesterol associated with the High Density Lipoprotein. LDL, Low Density Lipoprotein. LDL-Cholesterol, cholesterol associated with the Low Density Lipoprotein.
Bone Effects
Dual Energy X-ray Absorptiometry (DEXA) scans were performed in substudies of the Phase III clinical trials, primarily to evaluate changes in body fat distribution; changes in bone mineral density and content were also evaluated. Both treatment groups showed a small but statistically significant median decrease from baseline in bone mineral density (1.4% and 1.5% in the Edurant group and 1.4% and 1.5% in the efavirenz (control) group at Week 48 and Week 96, respectively), and bone mineral content (1.8% and 2.1% in the Edurant group and 2.0% and 2.5% in the efavirenz group at Week 48 and Week 96, respectively). These changes were not considered to be clinically relevant. No statistically significant differences were observed between treatment groups.
Fat Redistribution
As evaluated in the DEXA substudy, both treatment groups showed a small but statistically significant median increase from baseline in limb fat (11.6% and 10.9% in the Edurant and the control (efavirenz) group, respectively), trunk fat (15.5% and 13.9%, respectively), and total body fat (13.5% and 11.4%, respectively) at Week 96. No statistically significant differences were observed between treatment groups.
Patients Co-infected with Hepatitis B and/or Hepatitis C Virus
In HIV patients co-infected with hepatitis B and/or C virus receiving Edurant, the incidence of hepatic enzyme elevation was higher than in patients who were not co-infected. The pharmacokinetic exposure of rilpivirine in co-infected patients was comparable to that in patients without co-infection.
Electrocardiogram Findings
A pooled analysis of data from two Phase III clinical trials of antiretroviral-naïve HIV-1 infected patients who received either Edurant 25 mg once daily or control (efavirenz), showed statistically significant mean increase from baseline in the QTc interval at Weeks 48 and 96. During treatment with Edurant, the mean change from baseline in QTc increased through Week 48 without reaching plateau and remained stable between Week 48 and Week 96 (11.4 ms [95% CI 10.1, 12.8] and 12.4 ms [95% CI 11.0, 13.7], respectively). These trials excluded patients with high risk factors for proarrhythmia. The clinical relevance of these findings is unknown (see 7 WARNINGS AND PRECAUTIONS, Cardiovascular; 9.4 Drug-Drug Interactions, QT Prolonging Drugs; 10.2 Pharmacodynamics).
8.5 Post-Market Adverse Reactions
Adverse reactions have been identified during post-marketing in patients receiving a rilpivirine-containing regimen. Because these reactions are reported voluntarily from a population of unknown size, it is not always possible to reliably estimate their frequency or establish a causal relationship to drug exposure.
Renal and Genitourinary Disorders: nephrotic syndrome
Skin and Subcutaneous Tissue Disorders: severe skin and hypersensitivity reactions including DRESS (Drug Reaction with Eosinophilia and Systemic Symptoms)
9 DRUG INTERACTIONS
9.2 Drug Interactions Overview
Rilpivirine is primarily metabolized by cytochrome P450 (CYP)3A, and drugs that induce or inhibit CYP3A may thus affect the clearance of rilpivirine. Co-administration of Edurant and drugs that induce CYP3A or increase gastric pH may result in decreased plasma concentrations of rilpivirine and loss of virologic response and possible resistance to rilpivirine or to the NNRTI class of antiretrovirals. Co-administration of Edurant and drugs that inhibit CYP3A may result in increased plasma concentrations of rilpivirine.
9.4 Drug-Drug Interactions
Drugs that are contraindicated for co-administration with Edurant are included in Table 5. These recommendations are based on either drug interaction studies or predicted interactions due to the expected magnitude of interaction and the potential for loss of therapeutic effect.
Table 5: Drugs that Should Not Be Co-administered with Edurant
Concomitant Drug Class: Drug Name | Effect on Concentration of Rilpivirine or Concomitant Drug | Clinical Comment |
Anticonvulsants: carbamazepine, oxcarbazepine, phenobarbital, phenytoin | ↓ rilpivirine | Edurant is contraindicated with these anticonvulsants as co-administration may cause significant decreases in rilpivirine plasma concentrations (induction of CYP3A enzymes). This may result in loss of therapeutic effect of Edurant and possible development of resistance to Edurant and other NNRTIs. |
Antimycobacterials: rifampin1,2 rifapentine | ↓ rilpivirine ↔ rifampin ↔ rifapentine | Edurant is contraindicated with rifampin or rifapentine as co-administration may cause significant decreases in rilpivirine plasma concentrations (induction of CYP3A enzymes). This may result in loss of therapeutic effect of Edurant and possible development of resistance to Edurant and other NNRTIs. |
Glucocorticoids: dexamethasone (systemic) | ↓ rilpivirine ↔ dexamethasone | Edurant is contraindicated with systemic dexamethasone as co-administration may cause significant decreases in rilpivirine plasma concentrations (induction of CYP3A enzymes). This may result in loss of therapeutic effect of Edurant and possible development of resistance to Edurant and other NNRTIs. Alternatives should be considered, particularly for long-term use. |
Proton Pump Inhibitors: omeprazole1,2 lansoprazole, rabeprazole, pantoprazole, esomeprazole | ↓ rilpivirine ↓ omeprazole | Edurant is contraindicated with proton pump inhibitors as co-administration may cause significant decreases in rilpivirine plasma concentrations (increase in gastric pH). This may result in loss of therapeutic effect of Edurant and possible development of resistance to Edurant and other NNRTIs. |
Herbal Products: St. John’s wort (Hypericum perforatum) | ↓ rilpivirine | Edurant is contraindicated with products containing St. John’s wort (Hypericum perforatum) as co-administration may cause significant decreases in rilpivirine plasma concentrations (induction of CYP3A enzymes). This may result in loss of therapeutic effect of Edurant and possible development of resistance to Edurant and other NNRTIs. |
↑ = increase; ↓ = decrease; ↔ = no change
- 1. The interaction between Edurant and the drug was evaluated in a clinical study. All other drug-drug interactions shown are predicted.
- 2. This interaction study has been performed with a dose higher than the recommended dose for Edurant assessing the maximal effect on the co-administered drug. The dosing recommendation is applicable to the recommended dose of Edurant 25 mg once daily.
Established and other potentially significant drug interactions with Edurant are included in Table 6. These recommendations are based on either drug interaction studies or predicted interactions.
Table 6: Established and Other Potentially Significant Drug Interactions: Alterations in Dose or Regimen May Be Recommended Based on Drug Interaction Studies or Predicted Interaction (see Table 7 and Table 8)
Concomitant Drug Class: Drug Name | Effect on Concentration of Rilpivirine or Concomitant Drug | Clinical Comment |
| HIV-Antiviral Agents: Nucleoside Reverse Transcriptase Inhibitors (NRTIs) | ||
| Didanosine1,2 | ↔ rilpivirine ↔ didanosine | No dose adjustment is required when Edurant is co-administered with didanosine. Didanosine should be administered on an empty stomach and at least 2 hours before or at least four hours after Edurant (which should be administered with a meal). |
Other NRTIs (abacavir, emtricitabine, lamivudine, stavudine and zidovudine) | ↔ rilpivirine ↔ other NRTIs | Based on the different elimination routes for rilpivirine and these other NRTIs, no clinically relevant drug-drug interactions are expected between these drugs and Edurant. |
| HIV-Antiviral Agents: Non-nucleoside Reverse Transcriptase Inhibitors (NNRTIs) | ||
NNRTI (delavirdine) Other NNRTIs (efavirenz, etravirine, nevirapine) | ↑ rilpivirine ↔ delavirdine ↓ rilpivirine ↔ other NNRTIs | It is not recommended to co-administer Edurant with NNRTIs. |
| HIV-Antiviral Agents: Protease Inhibitors (PIs)—Boosted (i.e., with co-administration of low-dose ritonavir) or Unboosted (i.e., without co-administration of low-dose ritonavir) | ||
| darunavir/ritonavir1,2 | ↑ rilpivirine ↔ boosted darunavir | Concomitant use of Edurant with darunavir/ritonavir may cause an increase in the plasma concentrations of rilpivirine (inhibition of CYP3A enzymes). An interaction trial between rilpivirine (150 mg q.d.) and darunavir/ritonavir (800 mg/100 mg q.d.) demonstrated that darunavir/ritonavir increased the mean exposure of rilpivirine by 2.3-fold and from 2.7-fold to 3.8-fold in a subset (31%) of subjects. Caution should be exercised when these drugs are co-administered with Edurant. |
| lopinavir/ritonavir1,2 | ↑ rilpivirine ↔ boosted lopinavir | Concomitant use of Edurant with lopinavir/ritonavir may cause an increase in the plasma concentrations of rilpivirine (inhibition of CYP3A enzymes). An interaction trial between rilpivirine (150 mg q.d.) and lopinavir/ritonavir (400 mg/100 mg q.d.) demonstrated that lopinavir/ritonavir increased the mean exposure (AUC) of rilpivirine by 1.52-fold. Caution should be exercised when these drugs are co-administered with Edurant. |
| other boosted PIs (atazanavir/ritonavir, fosamprenavir/ritonavir, saquinavir/ritonavir, tipranavir/ritonavir) | ↑ rilpivirine ↔ boosted PI | Concomitant use of Edurant with boosted PIs may cause an increase in the plasma concentrations of rilpivirine (inhibition of CYP3A enzymes). Edurant is not expected to affect the plasma concentrations of co-administered PIs. |
| unboosted PIs (atazanavir, fosamprenavir, indinavir, nelfinavir) | ↑ rilpivirine ↔ unboosted PI | Concomitant use of Edurant with unboosted PIs may cause an increase in the plasma concentrations of rilpivirine (inhibition of CYP3A enzymes). Edurant is not expected to affect the plasma concentrations of co-administered PIs. |
| HIV-Antiviral Agents: CCR5 Antagonists | ||
| maraviroc | ↔ rilpivirine ↔ maraviroc | No clinically relevant drug-drug interaction is expected when Edurant is co-administered with maraviroc. |
| HIV-Antiviral Agents: Integrase Strand Transfer Inhibitors | ||
| raltegravir | ↔ rilpivirine ↔ raltegravir | No dose adjustment is required when Edurant is co-administered with raltegravir. |
| Other Antiviral Agents | ||
| ribavirin Simeprevir*1 | ↔ rilpivirine ↔ ribavirin ↔ rilpivirine ↔ simeprevir | No clinically relevant drug-drug interaction is expected when Edurant is co-administered with ribavirin. No dose adjustment is required for either drug when Edurant is co-administered with simeprevir. |
| Other Agents | ||
Antacids: antacids (e.g., aluminum or magnesium hydroxide, calcium carbonate) | ↔ rilpivirine | The combination of Edurant and antacids should be used with caution as co-administration may cause significant decreases in rilpivirine plasma concentrations (increase in gastric pH). Antacids should only be administered either at least 2 hours before or at least 4 hours after Edurant. |
Antiarrhythmics: digoxin | ↔ rilpivirine ↔ digoxin | No dose adjustment is required when Edurant is co-administered with digoxin. |
Antidiabetics: metformin | ↔ rilpivirine ↔ metformin | Co-administration of Edurant with metformin produced no changes in plasma concentration of metformin. No dose adjustment is required when Edurant is co-administered with metformin. |
Antimycobacterials: rifabutin1,2 | ↓ rilpivirine ↔ rifabutin | Concomitant use of Edurant with rifabutin may cause significant decreases in rilpivirine plasma concentrations (induction of CYP3A enzymes). This may result in loss of therapeutic effect of Edurant. Throughout co-administration of Edurant with rifabutin, the Edurant dose should be increased from 25 mg once daily to 50 mg once daily. When rifabutin co-administration is stopped, the Edurant dose should be decreased to 25 mg once daily. |
Azole Antifungal Agents: ketoconazole1,2 fluconazole itraconazole posaconazole voriconazole | ↑ rilpivirine ↓ ketoconazole | Concomitant use of Edurant with azole antifungal agents may cause an increase in the plasma concentrations of rilpivirine (inhibition of CYP3A enzymes). An interaction trial between rilpivirine (150 mg q.d.) and ketoconazole (400 mg q.d.) demonstrated that ketoconazole increased the mean exposure of rilpivirine by 1.49-fold. The concomitant use of Edurant with other azole antifungals is expected to result in increased mean exposure (AUC) of rilpivirine (see QT prolonging drugs). Caution should be exercised when these drugs are co-administered with Edurant. Clinical monitoring for breakthrough infections is recommended when azole antifungals are co-administered with Edurant. |
HMG-CoA Reductase Inhibitors atorvastatin1,2 pravastatin rosuvastatin simvastatin | ↔ rilpivirine ↔ atorvastatin | No dose adjustment is required when Edurant is co-administered with HMG-CoA reductase inhibitors. |
H2-Receptor Antagonists: famotidine1,2 cimetidine nizatidine ranitidine | ↔ rilpivirine (famotidine taken 12 hours before rilpivirine) ↓ rilpivirine (famotidine taken 2 hours before rilpivirine) ↔ rilpivirine (famotidine taken 4 hours after rilpivirine) | The combination of Edurant and H2-receptor antagonists should be used with caution as co-administration may cause significant decreases in rilpivirine plasma concentrations (increase in gastric pH). H2-receptor antagonists should only be administered at least 12 hours before or at least 4 hours after Edurant. |
Macrolide Antibiotics: clarithromycin, erythromycin | ↑ rilpivirine ↔ clarithromycin ↔ erythromycin | Concomitant use of Edurant with clarithromycin or erythromycin may cause an increase in the plasma concentrations of rilpivirine (inhibition of CYP3A enzymes). Where possible, alternatives such as azithromycin should be considered. |
Narcotic Analgesics: methadone1 | ↓ R(-) methadone ↓ S(+) methadone | No dose adjustments are required when initiating co-administration of methadone with Edurant. However, clinical monitoring is recommended as methadone maintenance therapy may need to be adjusted in some patients. |
PDE-5 Inhibitors: sildenafil1,2 tadalafil vardenafil | ↔ sildenafil | No dose adjustment is required when Edurant is co-administered with PDE-5 inhibitors used in dosage regimens for the treatment of erectile dysfunction or pulmonary arterial hypertension. |
↑ = increase; ↓ = decrease; ↔ = no change
- 1. The interaction between Edurant and the drug was evaluated in a clinical study. All other drug-drug interactions shown are predicted.
- 2. This interaction study has been performed with a dose higher than the recommended dose for Edurant assessing the maximal effect on the co-administered drug. The dosing recommendation is applicable to the recommended dose of Edurant 25 mg once daily.
Drug interaction studies were performed with Edurant and other drugs likely to be co-administered or commonly used as probes for pharmacokinetic interactions. The effects of co-administration of other drugs on the Cmax, AUC, and Cmin values of rilpivirine are summarized in Table 7 (effect of other drugs on Edurant). The effect of co-administration of Edurant on the Cmax, AUC, and Cmin values of other drugs are summarized in Table 8 (effect of Edurant on other drugs).
Table 7: Drug Interactions: Pharmacokinetic Parameters for Rilpivirine in the Presence of Co-administered Drugs
| Co-administered Drug | Dose/Schedule | N | Exposure | Mean Ratio of Rilpivirine Pharmacokinetic Parameters With/Without Co-administered Drug (90% CI); No Effect = 1.00 | ||||||||||||||
|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|
Co-administered Drug | Rilpivirine | Cmax | AUC | Cmin | ||||||||||||||
| Co-administration With HIV Protease Inhibitors (PIs) | ||||||||||||||||||
| Darunavir/ritonavir | 800/100 mg q.d. | 150 mg q.d.2 | 14 | ↑ | 1.79 (1.56-2.06) | 2.30 (1.98-2.67) | 2.78 (2.39-3.24) | |||||||||||
| Lopinavir/ritonavir (soft gel capsule) | 400/100 mg b.i.d. | 150 mg q.d.2 | 15 | ↑ | 1.29 (1.18-1.40) | 1.52 (1.36-1.70) | 1.74 (1.46-2.08) | |||||||||||
| Co-administration with HIV Nucleoside or Nucleotide Reverse Transcriptase Inhibitors (NRTIs/N[t]RTIs) | ||||||||||||||||||
| Didanosine | 400 mg q.d. | 150 mg q.d.2 | 21 | ↔ | 1.00 (0.90-1.10) | 1.00 (0.95-1.06) | 1.00 (0.92-1.09) | |||||||||||
Tenofovir disoproxil fumarate | 300 mg q.d. | 150 mg q.d.2 | 16 | ↔ | 0.96 (0.81-1.13) | 1.01 (0.87-1.18) | 0.99 (0.83-1.16) | |||||||||||
| Co-administration with HIV Integrase Strand Inhibitors | ||||||||||||||||||
| Raltegravir | 400 mg b.i.d. | 25 mg q.d. | 23 | ↔ | 1.12 (1.04-1.20) | 1.12 (1.05-1.19) | 1.03 (0.96-1.12) | |||||||||||
| Co-administration with other Antivirals | ||||||||||||||||||
| Simeprevir | 150 mg q.d. | 25 mg q.d. | 23 | ↔ | 1.04 (0.95-1.13) | 1.12 (1.05-1.19) | 1.25 (1.16-1.35) | |||||||||||
| Co-administration with Drugs other than Antiretrovirals | ||||||||||||||||||
| Acetaminophen | 500 mg single dose | 150 mg q.d.2 | 16 | ↔ | 1.09 (1.01-1.18) | 1.16 (1.10-1.22) | 1.26 (1.16-1.38) | |||||||||||
| Atorvastatin | 40 mg q.d. | 150 mg q.d.2 | 16 | ↔ | 0.91 (0.79-1.06) | 0.90 (0.81-0.99) | 0.90 (0.84-0.96) | |||||||||||
| Ethinylestradiol/ Norethindrone | 0.035 mg q.d./ 1 mg q.d. | 25 mg q.d. | 15 | ↔ | ↔1 | ↔1 | ↔1 | |||||||||||
| Famotidine | 40 mg single dose taken 12 hours before rilpivirine | 150 mg single dose2 | 24 | ↔ | 0.99 (0.84-1.16) | 0.91 (0.78-1.07) | N.A. | |||||||||||
| Famotidine | 40 mg single dose taken 2 hours before rilpivirine | 150 mg single dose2 | 23 | ↓ | 0.15 (0.12-0.19) | 0.24 (0.20-0.28) | N.A. | |||||||||||
| Famotidine | 40 mg single dose taken 4 hours after rilpivirine | 150 mg single dose2 | 24 | ↔ | 1.21 (1.06-1.39) | 1.13 (1.01-1.27) | N.A. | ||||||
|---|---|---|---|---|---|---|---|---|---|---|---|---|---|
| Ketoconazole | 400 mg q.d. | 150 mg q.d.2 | 15 | ↑ | 1.30 (1.13-1.48) | 1.49 (1.31-1.70) | 1.76 (1.57-1.97) | ||||||
| Methadone | 60-100 mg q.d., individualized dose | 25 mg q.d. | 12 | ↔ | ↔1 | ↔1 | ↔1 | ||||||
| Omeprazole | 20 mg q.d. | 150 mg q.d.2 | 16 | ↓ | 0.60 (0.48-0.73) | 0.60 (0.51-0.71) | 0.67 (0.58-0.78) | ||||||
| Rifabutin | 300 mg q.d. | 25 mg q.d. | 18 | ↓ | 0.69 (0.62-0.76) | 0.58 (0.52-0.65) | 0.52 (0.46-0.59) | ||||||
| Rifabutin | 300 mg q.d. | 50 mg q.d.2 | 18 | ↔ | 1.43 (1.30-1.56) | 1.16 (1.06-1.26) | 0.93 (0.851.01) | ||||||
| (as compared to 25 mg q.d. rilpivirine alone) | |||||||||||||
| Rifampin | 600 mg q.d. | 150 mg q.d.2 | 16 | ↓ | 0.31 (0.27-0.36) | 0.20 (0.18-0.23) | 0.11 (0.10-0.13) | ||||||
| Sildenafil | 50 mg single dose | 75 mg q.d.2 | 16 | ↔ | 0.92 (0.85-0.99) | 0.98 (0.92-1.05) | 1.04 (0.98-1.09) | ||||||
CI = confidence interval; N = maximum number of subjects with data; N.A. = not available; ↑ = increase; ↓= decrease; ↔ = no change; q.d. = once daily; b.i.d. = twice daily
- 1. comparison based on historic controls
- 2. This interaction study has been performed with a dose higher than the recommended dose for Edurant (25 mg once daily) assessing the maximal effect on the co-administered drug.
Table 8: Drug Interactions: Pharmacokinetic Parameters for Co-administered Drugs in the Presence of Edurant
| Co-administered Drug | Dose/Schedule | N | Exposure | Mean Ratio of Co-administered Drug Pharmacokinetic Parameters With/Without Edurant (90% CI); No Effect = 1.00 | ||||||||||
|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|
| Co-administered Drug | Rilpivirine | Cmax | AUC | Cmin | ||||||||||
| Co-Administration with HIV Protease Inhibitors (PIs) | ||||||||||||||
| Darunavir/ritonavir | 800/100 mg q.d. | 150 mg q.d.1 | 15 | ↔ | 0.90 (0.81-1.00) | 0.89 (0.81-0.99) | 0.89 (0.68-1.16) | |||||||
| Lopinavir/ritonavir (soft gel capsule) | 400/100 mg b.i.d. | 150 mg q.d.1 | 15 | ↔ | 0.96 (0.88-1.05) | 0.99 (0.89-1.10) | 0.89 (0.73-1.08) | |||||||
| Co-Administration with HIV Nucleoside or Nucleotide Reverse Transcriptase Inhibitors (NRTIs/N[t]RTIs) | ||||||||||||||
| Didanosine | 400 mg q.d. | 150 mg q.d.1 | 13 | ↔ | 0.96 (0.80-1.14) | 1.12 (0.99-1.27) | N.A. | |||||||
| Tenofovir disoproxil fumarate | 300 mg q.d. | 150 mg q.d.1 | 16 | ↑ | 1.19 (1.06-1.34) | 1.23 (1.16-1.31) | 1.24 (1.10-1.38) | |||||||
| Co-administration with HIV Integrase Strand Inhibitors | ||||||||||||
|---|---|---|---|---|---|---|---|---|---|---|---|---|
| Raltegravir | 400 mg b.i.d. | 25 mg q.d. | 23 | ↑ | 1.10 (0.77-1.58) | 1.09 (0.81-1.47) | 1.27 (1.01-1.60) | |||||
| Co-administration with other Antivirals | ||||||||||||
| Simeprevir | 150 mg q.d. | 25 mg q.d. | 21 | ↔ | 1.10 (0.97-1.26) | 1.06 (0.94-1.19) | 0.96 (0.83-1.11) | |||||
| Co-Administration with Drugs other than Antiretrovirals | ||||||||||||
| Acetaminophen | 500 mg single dose | 150 mg q.d.1 | 16 | ↔ | 0.97 (0.86-1.10) | 0.91 (0.86-0.97) | N.A. | |||||
| Atorvastatin | 40 mg q.d. | 150 mg q.d.1 | 16 | ↔ | 1.35 (1.08-1.68) | 1.04 (0.97-1.12) | 0.85 (0.69-1.03) | |||||
| Digoxin | 0.5 mg single dose | 25 mg q.d. | 22 | ↔ | 1.06 (0.97-1.17) | 0.98 (0.93-1.04)2 | N.A. | |||||
| Ethinylestradiol Norethindrone | 0.035 mg q.d. 1 mg q.d. | 25 mg q.d. | 17 17 | ↔ ↔ | 1.17 (1.06-1.30) 0.94 (0.83-1.06) | 1.14 (1.10-1.19) 0.89 (0.84-0.94) | 1.09 (1.03-1.16) 0.99 (0.90-1.08) | |||||
| Ketoconazole | 400 mg q.d. | 150 mg q.d.1 | 14 | ↓ | 0.85 (0.80-0.90) | 0.76 (0.70-0.82) | 0.34 (0.25-0.46) | |||||
R(-) methadone S(+) methadone | 60-100 mg q.d., individualised dose | 25 mg q.d. | 13 13 | ↓ ↓ | 0.86 (0.78-0.95) 0.87 (0.78-0.97) | 0.84 (0.74-0.95) 0.84 (0.74-0.96) | 0.78 (0.67-0.91) 0.79 (0.67-0.92) | |||||
| Metformin | 850 mg single dose | 25 mg q.d. | 20 | ↔ | 1.02 (0.95-1.10) | 0.97 (0.90-1.06) | N.A. | |||||
| Omeprazole | 20 mg q.d. | 150 mg q.d.1 | 15 | ↓ | 0.86 (0.68-1.09) | 0.86 (0.76-0.97) | N.A. | |||||
| Rifabutin 25-O-desacetylrifabutin | 300 mg q.d. | 150 mg q.d.1 | 17 17 | ↔ ↔ | 1.03 (0.93-1.14) 1.07 (0.98-1.17) | 1.03 (0.97-1.09) 1.07 (1.02-1.11) | 1.01 (0.94-1.09) 1.12 (1.03-1.22) | |||||
Rifampin 25-desacetylrifampin | 600 mg q.d. | 150 mg q.d.1 | 16 16 | ↔ ↔ | 1.02 (0.93-1.12) 1.00 (0.87-1.15) | 0.99 (0.92-1.07) 0.91 (0.77-1.07) | N.A. N.A. | |||||
| Sildenafil | 50 mg single dose | 75 mg q.d.1 | 16 | ↔ | 0.93 (0.80-1.08) | 0.97 (0.87-1.08) | N.A. | |||||
CI = confidence interval; N = maximum number of subjects with data; N.A. = not available; ↑ = increase; ↓ = decrease; ↔ = no change; q.d. = once daily; b.i.d. = twice daily
- 1. This interaction study has been performed with a dose higher than the recommended dose for Edurant (25 mg once daily) assessing the maximal effect on the co-administered drug.
- 2. AUClast
QT Prolonging Drugs
There is limited information available on the potential for a pharmacodynamic interaction between rilpivirine and drugs that prolong the QTc interval. In a Phase I study of healthy subjects, rilpivirine at doses of 75 mg and 300 mg once daily was shown to prolong the QTc interval of the electrocardiogram.
Edurant is a substrate for CYP3A4. Plasma levels of rilpivirine can be increased by inhibitors of CYP3A4. Drugs that inhibit CYP3A4 include, but are not limited to, indinavir, ritonavir, nelfinavir, saquinavir, azole antifungal agents (e.g., ketoconazole, fluconazole, voriconazole), clarithromycin, erythromycin, and telithromycin. Caution should be observed if these drugs are to be used concomitantly with Edurant.
Caution should be observed when using Edurant with drugs that can disrupt electrolyte levels, including, but not limited to, the following: loop, thiazide, and related diuretics; laxatives and enemas; amphotericin B; high dose corticosteroids.
Edurant should be used with caution when co-administered with a drug with a known risk of Torsade de Pointes (see 7 WARNINGS AND PRECAUTIONS, Cardiovascular).
9.5 Drug-Food Interactions
The exposure to rilpivirine was approximately 40% lower when Edurant was taken in a fasted condition as compared to a normal caloric meal (533 kcal) or a high-fat high-caloric meal (928 kcal). When Edurant was taken with only a protein-rich nutritional drink, exposures were 50% lower than when taken with a meal. These decreases in plasma concentrations of rilpivirine may result in a loss of virologic response and possible resistance to Edurant and the NNRTI class of antiretrovirals.
Grapefruit or grapefruit juice can inhibit CYP3A enzyme activity and should be avoided with Edurant.
9.6 Drug-Herb Interactions
Edurant should not be used in combination with products containing St. John’s wort as co-administration may cause significant decreases in rilpivirine plasma concentrations (induction of CYP3A enzymes). This may result in loss of therapeutic effect of Edurant (see Table 5).
9.7 Drug-Laboratory Test Interactions
Interactions with laboratory tests have not been established.
10 CLINICAL PHARMACOLOGY
10.1 Mechanism of Action
Rilpivirine is a diarylpyrimidine NNRTI of human immunodeficiency virus type 1 (HIV-1). Rilpivirine activity is mediated by non-competitive inhibition of HIV-1 reverse transcriptase (RT). Rilpivirine does not inhibit the human cellular DNA polymerases α, β and γ.
10.2 Pharmacodynamics
Effect on Electrocardiogram
The effect of Edurant on the QTc interval of the ECG was evaluated in two Phase I studies in healthy adult volunteers. Edurant at the recommended therapeutic dose of 25 mg q.d. was examined in a double-blind, double-dummy, randomized, placebo- and active-controlled, three-way crossover study in healthy adult volunteers (N=60, 35M/25F), with 13 ECG recordings over 24 hours on day 11 of treatment (steady-state). Edurant at the dose of 25 mg q.d. was not associated with a statistically significant or clinically relevant effect on the QTc interval. Edurant at doses of 75 mg q.d., and 300 mg q.d. was studied in a double-blind, double-dummy, randomized, placebo and active controlled, three-way crossover study in healthy adult volunteers (N=41, 22F/19M), with 13 ECG recordings over 24 hours on day 1 and day 11 of treatment. On day 11 of treatment (steady-state), the maximum mean QTc interval prolongation (baseline- and placebo-adjusted) was 10.7 (90% CI 6.1, 15.3) ms in the 75 mg q.d. treatment arm and 23.3 (90% CI 18.0, 28.7) ms at 4.5 h post-dosing in the 300 mg q.d. arm.
For QTc interval effects with long-term treatment in the target patient population see 8.4 Abnormal Laboratory Findings: Hematologic, Clinical Chemistry and Other Quantitative Data, Electrocardiogram Findings. See also 7 WARNINGS AND PRECAUTIONS, Cardiovascular and 9.4 Drug-Drug Interactions, QT Prolonging Drugs.
Safety Pharmacology Study
Concentration-dependent inhibition of potassium-currents involved in the repolarisation of the cardiac action potential and prolongation of QT interval from baseline in arterially perfused rabbit left ventricular wedge preparations were observed in the in vitro safety pharmacology studies.
In an antibody-based chemoluminescent assay, rilpivirine was found to decrease the surface expression of hERG potassium channels by 29% and 36% at nominal concentrations of 3.7 and 11.0 μg/mL.
10.3 Pharmacokinetics
The pharmacokinetic properties of rilpivirine have been evaluated in adult healthy subjects and in antiretroviral treatment-naïve HIV-1-infected subjects 12 years of age and older. Exposure to rilpivirine was generally lower in HIV-1 infected subjects than in healthy subjects.
Table 9: Population Pharmacokinetic Estimates of Rilpivirine 25 mg Once Daily in Antiretroviral Treatment-Naïve HIV-1-Infected Subjects (Pooled Data from Phase III Trials at Week 48)
| Parameter | Rilpivirine 25 mg once daily N=679 |
| AUC24h (ng•h/mL) | |
| Mean ± Standard Deviation | 2397 ± 1032 |
| Median (Range) | 2204 (482-8601) |
| C0h (ng/mL) | |
| Mean ± Standard Deviation | 80 ± 37 |
| Median (Range) | 74 (1-300) |
Absorption: After oral administration, the maximum plasma concentration of rilpivirine is generally achieved within 4-5 hours. Steady-state plasma concentrations are reached in approximately 11 days. In a number of healthy subjects, multiple absorption peaks and/or an increase in absorption between 12 hours and 24 hours post-dose is observed. The underlying mechanism(s) for these observations is unknown. The absolute bioavailability of Edurant is unknown.
Effect of food on absorption
The exposure to rilpivirine was approximately 40% lower when Edurant was taken in a fasted condition as compared to a normal caloric meal (533 kcal) or high-fat high-caloric meal (928 kcal). When Edurant was taken with only a protein-rich nutritional drink, exposures were 50% lower than when taken with a meal. Therefore, to achieve optimal exposure, Edurant should be taken with a meal (see 4.4 Administration).
Distribution: Rilpivirine is approximately 99.7% bound to plasma proteins in vitro, primarily to albumin. The distribution of rilpivirine into compartments other than plasma (e.g., cerebrospinal fluid, genital tract secretions) has not been evaluated in humans.
Metabolism: In vitro experiments indicate that rilpivirine primarily undergoes oxidative metabolism mediated by the cytochrome P450(CYP)3A system.
Elimination: The terminal elimination half-life of rilpivirine is approximately 45 hours. After single-dose oral administration of 14C-rilpivirine, on average 85% and 6.1% of the radioactivity could be retrieved in feces and urine, respectively. In feces, unchanged rilpivirine accounted for on average 25% of the administered dose. Only trace amounts of unchanged rilpivirine (<1% of dose) were detected in urine.
Special Populations and Conditions
Pediatrics:
The pharmacokinetics of rilpivirine in antiretroviral treatment naïve HIV-1 infected pediatric subjects 12 to less than 18 years of age receiving Edurant 25 mg once daily were comparable to those in treatment-naive HIV-1 infected adults receiving Edurant 25 mg once daily. There was no clinically significant impact of body weight on rilpivirine pharmacokinetics in pediatric subjects in trial C213 (33 to 93 kg).
The safety and efficacy of Edurant in pediatric patients less than 12 years of age has not been established.
Geriatrics:
Clinical studies of Edurant did not include sufficient numbers of subjects aged 65 and over to determine whether they respond differently from adult subjects < 65 years of age. Edurant should be used with caution in this population (see 7.1.4 Geriatrics).
Sex:
Population pharmacokinetic analysis of rilpivirine in HIV-infected patients indicated no clinically relevant differences in the pharmacokinetics of rilpivirine between men and women.
Age:
Population pharmacokinetic analysis of rilpivirine in HIV-infected patients indicated no clinically relevant differences in the pharmacokinetics of rilpivirine across the age range of 18-78 years (the analysis included only two subjects above 65 years)
Pregnancy and Breast-feeding:
The exposure to total rilpivirine after intake of rilpivirine 25 mg once daily as part of an antiretroviral regimen was lower during pregnancy (similar for the 2nd and 3rd trimester) compared with postpartum (see Table 10). The decrease in unbound (i.e., active) rilpivirine pharmacokinetic parameters during pregnancy compared to postpartum was less pronounced than for total rilpivirine.
In women receiving rilpivirine 25 mg once daily during the 2nd trimester of pregnancy, mean intra-individual values for total rilpivirine Cmax, AUC24h and Cmin values were, respectively, 21%, 29% and 35% lower as compared to postpartum; during the 3rd trimester of pregnancy, Cmax, AUC24h and Cmin values were, respectively, 20%, 31% and 42% lower as compared to postpartum.
Table 10: Pharmacokinetic Results of Total Rilpivirine After Administration of Rilpivirine 25 mg Once Daily as Part of an Antiretroviral Regimen, During the 2nd Trimester of Pregnancy, the 3rd Trimester of Pregnancy and Postpartum
Pharmacokinetics of total rilpivirine (mean ±SD, tmax: median [range]) | Postpartum (6-12 Weeks) (n=11) | 2nd Trimester of pregnancy (n=15) | 3rd Trimester of pregnancy (n=13) |
| Cmin, ng/mL | 84.0 ± 58.8 | 54.3 ± 25.8 | 52.9 ± 24.4 |
| Cmax, ng/mL | 167 ± 101 | 121 ±45.9 | 123 ± 47.5 |
| tmax, h | 4.00 (2.03-25.08) | 4.00 (1.00-9.00) | 4.00 (2.00-24.93) |
| AUC24h, ng•h/mL | 2714 ± 1535 | 1792 ± 711 | 1762 ± 662 |
Ethnic origin:
Population pharmacokinetic analysis of rilpivirine in HIV-infected patients indicated that race had no clinically relevant effect on the pharmacokinetics of rilpivirine.
Hepatic Insufficiency:
Rilpivirine is primarily metabolized and eliminated by the liver. In a study comparing 8 subjects with mild hepatic impairment (Child-Pugh score A) to 8 matched controls, and 8 subjects with moderate hepatic impairment (Child-Pugh score B) to 8 matched controls, the multiple dose exposure of rilpivirine was 47% higher in subjects with mild hepatic impairment and 5% higher in subjects with moderate hepatic impairment. Edurant has not been studied in subjects with severe hepatic impairment (Child-Pugh score C) (see 7 WARNINGS AND PRECAUTIONS, Hepatic Impairment and 4.2 Recommended Dose and Dosage Adjustment, Hepatic Impairment).
Hepatitis B or Hepatitis C Virus Co-infection
Population pharmacokinetic analysis indicated that hepatitis B and/or C virus co-infection had no clinically relevant effect on the exposure to rilpivirine.
Renal Insufficiency:
The pharmacokinetics of rilpivirine have not been studied in patients with renal insufficiency. Renal elimination of rilpivirine is negligible. Therefore, the impact of renal impairment on rilpivirine elimination is expected to be minimal. As 99.7% of rilpivirine is bound to plasma, it is unlikely that it will be significantly removed by hemodialysis or peritoneal dialysis (see 7 WARNINGS AND PRECAUTIONS, Renal Impairment and 4.2 Recommended Dose and Dosage Adjustment, Renal Impairment).
11 STORAGE, STABILITY AND DISPOSAL
Store Edurant tablets between 15–30°C. Store in the original bottle and protect from light.
12 SPECIAL HANDLING INSTRUCTIONS
No special handling instructions are required for this product.
PART II: SCIENTIFIC INFORMATION
13 PHARMACEUTICAL INFORMATION
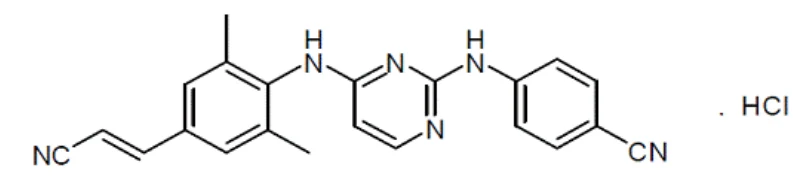
Drug Substance
Proper name: rilpivirine hydrochloride
Chemical name: 4-[[4-[[4-[(E)-2-cyanoethenyl]-2,6-dimethylphenyl]amino]-2-pyrimidinyl]amino]benzonitrile monohydrochloride
Molecular formula and molecular mass: C22 H18 N6 . HCl
402.88 – rilpivirine hydrochloride
366.42 – rilpivirine
Structural formula:
Physicochemical properties:
Description: Rilpivirine hydrochloride is a white to almost white powder.
Solubility: Rilpivirine hydrochloride is practically insoluble in water over a wide pH range.
pKa: The pKa is 5.6 (pyrimidine moiety)
14 CLINICAL TRIALS
14.1 Clinical Trials by Indication
Treatment-Naïve Adult Patients
Trial TMC278-C209 (ECHO) and TMC278-C215 (THRIVE)
The evidence of efficacy of EDURANT® (rilpivirine) is based on the analyses of 48 and 96-week data from two Phase III trials in antiretroviral treatment-naïve HIV-1 infected adult subjects (Table 11). Similar efficacy for Edurant was seen in each trial demonstrating non-inferiority to efavirenz.
Subjects with plasma HIV-1 RNA ≥5000 copies/mL, who were screened for susceptibility to N(t)RTIs and for absence of specific NNRTI RAMs, were included in the trials. The treatments are summarized in Table 11.
Table 11: Study Design, Dosage and Administration in the Treatment and Active Control Arms, and Type of Background Regimens used in Antiretroviral Treatment-Naïve HIV-1 Infected Adult Patients in Studies TMC278-C209 (ECHO) and TMC278-C215 (THRIVE)
| Study | Edurant + BR | Efavirenz + BR (Control) |
|---|---|---|
TMC278-C209 (ECHO) Phase III, randomized, double-blind, active control, multicentre. | Edurant1 25 mg (Oral) once daily BR3, Tenofovir disoproxil fumarate (TDF) plus emtricitabine (FTC) | Efavirenz2 600 mg (Oral) once daily BR3, Tenofovir disoproxil fumarate (TDF) plus emtricitabine (FTC) |
TMC278-C215 (THRIVE) Phase III, randomized, double-blind, active control, multicentre. | Edurant1 25 mg (Oral) once daily BR4, Tenofovir disoproxil fumarate (TDF) plus emtricitabine (FTC), or
| Efavirenz2 600 mg (Oral) once daily BR4, Tenofovir disoproxil fumarate (TDF) plus emtricitabine (FTC) or
|
- 1. See 4 DOSAGE AND ADMINISTRATION section for complete guidance on clinical usage.
- 2. See efavirenz (SUSTIVA) Product Monograph for additional information.
- 3. BR = Background regimen. See TRUVADA Product Monograph or the individual Product Monographs of EMTRIVA or VIREAD for complete guidance on the dosage and administration of background regimens.
- 4. BR = Background regimen. The choice of background regimen was at the discretion of the investigator. See Product Monographs of the individual drugs for complete guidance on dosage and administration
In the pooled analyses of TMC278-C209 and TMC278-C215 the demographic and baseline disease characteristics were balanced between the Edurant arm and efavirenz (control) arms (Table 12).
Table 12: Demographic and Baseline Disease Characteristics of Antiretroviral Treatment-Naïve HIV-1 Infected Adult Patients in Studies TMC278-C209 (ECHO) and TMC278-C215 (THRIVE), Pooled Analysis
| Pooled Data from Trials TMC278-C209 and TMC278-C215 | ||||||||
|---|---|---|---|---|---|---|---|---|
Edurant + BR N=686 | Efavirenz + BR N=682 | |||||||
| Demographic Characteristics | ||||||||
| Medium Age, years (range) | 36 (18-78) | 36 (19-69) | ||||||
| Sex | ||||||||
| Male | 76% | 76% | ||||||
| Female | 24% | 24% | ||||||
| Race | ||||||||
| White | 61% | 60% | ||||||
| Black/African American | 24% | 23% | ||||||
| Asian | 11% | 14% | ||||||
| Other | 2% | 2% | ||||||
| Not allowed to ask per local | 1% | 1% | ||||||
| Pooled Data from Trials TMC278-C209 and TMC278-C215 | ||||||||||
|---|---|---|---|---|---|---|---|---|---|---|
Edurant + BR N=686 | Efavirenz + BR N=682 | |||||||||
| regulations | ||||||||||
| Baseline Disease Characteristics | ||||||||||
| Median Baseline Plasma HIV-1 RNA (range), Log10 copies/ml. | 5.0 (2-7) | 5.0 (3-7) | ||||||||
| Percent of Patients with Baseline Plasma Viral Load; ≤ 100,000 > 100,000 to ≤ 500,000 > 500,000 | 54% 36% 10% | 48% 40% 12% | ||||||||
| Median Baseline CD4+ Cell Count (range), cells/mm3 | 249 (1-888) | 260 (1-1137) | ||||||||
| Percent of Patients with Hepatitis B/C Virus Co-infection | 7% | 10% | ||||||||
Percent of Patients with the following background regimens:
| 80% 15% 5% | 80% 15% 5% | ||||||||
BR = Background regimen
Efficacy at Week 48 and Week 96 for subjects in the Edurant and efavirenz arms for the pooled data from the TMC278-C209 and TMC278-C215 study populations are shown in Table 13. The response rate (confirmed undetectable viral load <50 HIV-1 RNA copies/mL) at Week 96 was comparable between the Edurant arm and the efavirenz arm. The incidence of virologic failure was higher in the Edurant arm than the efavirenz arm at Week 96; however, most of the virologic failures occurred within the first 48 weeks of treatment. Discontinuations due to adverse events were higher in the efavirenz arm than the Edurant arm.
Table 13: Virologic Outcome of Randomized Treatment in the TMC278-C209 (ECHO) and TMC278-C215 (THRIVE) Trials in Adults (Pooled Analysis at Week 48 and Week 96; ITT-TLOVR1)
| Outcomes | Outcome at Week 48 | Outcome at Week 96 | ||||||||
Edurant + BR N=686 | Efavirenz + BR N=682 | Edurant + BR N=686 | Efavirenz + BR N=682 | |||||||
Confirmed Undetectable Viral Load (<50 HIV-1 RNA copies/mL) 2,3 Overall ≤ 100,000 > 100,000 | 84.3% 90.2% 77.4% | 82.3% 83.6% 81.0% | 77.6% 84.0% 70.1% | 77.6% 79.9% 75.4% | ||||||
Virologic Failure5 Overall ≤ 100,000 > 100,000 | 9.0% 3.8% 15.1% | 4.8% 3.3% 6.3% | 11.5% 5.7% 18.2% | 5.9% 3.6% 7.9% |
| Death | 0.1% | 0.4% | 0.1% | 0.9% |
| Discontinued due to adverse event (AE) | 2.0% | 6.7% | 3.8% | 7.6% |
| Discontinued for non-AE reason4 | 4.5% | 5.7% | 7.0% | 8.1% |
N = number of subjects per treatment group BR = Background regimen
- 1. ITT, Intent-to-treat time to loss of virologic response
- 2. Subjects achieved virologic response (two consecutive viral loads <50 copies/mL) and maintained it through Week 48/96.
- 3. Predicted difference of response rates (95% CI) at Week 48: 1.6% (2.2%; 5.3%) and at week 96: -0.4% (- 4.6%; 3.8%); both p values <0.0001 (non-inferiority at 12% margin) from logistic regression model, including stratification factors and study.
- 4. e.g., lost to follow-up, non-compliance, withdrew consent
- 5. Virologic failure in pooled efficacy analysis: includes subjects who were rebounder (confirmed viral load ≥50 copies/mL after being responder) or who were never suppressed (no confirmed viral load <50 copies/mL, either ongoing or discontinued due to lack or loss of efficacy).
At week 48, the mean change from baseline in CD4+ cell count was 192 cells/mm3 in the Edurant-treated subjects and 176 cells/mm3 in the efavirenz-treated subjects in the pooled analysis of the ECHO and THRIVE trials [estimated treatment difference (95% CI): 18.0 (2.2; 33.7)].
At week 96, the mean change from baseline in CD4+ cell count was 228 cells/mm3 in the Edurant-treated subjects and 219 cells/mm3 in the efavirenz-treated subjects [estimated treatment difference (95% CI): 11.3 (-6.8; 29.4)].
A subgroup analysis of the virological response (<50 HIV-1 RNA copies/mL, TLOVR) at 48 and 96 weeks by background NRTIs, and by CD4+ cell count, and virological failure by CD4+ cell count (pooled data from the TMC278-C209 and TMC278-C215 trials) is presented in Table 14.
Table 14: Subgroup Outcomes (ITT-TLOVR) at Week 48 (Primary) and Week 96 in the Pooled TMC278-C209 (ECHO) and TMC278-C215 (THRIVE) Trials in Adults, by Background NRTI, and Baseline CD4+ Cell Count
Week-48 Outcomes HIV-RNA (<50 copies/mL) | Week-96 Outcomes HIV-RNA (<50 copies/mL) | |||||||||
|---|---|---|---|---|---|---|---|---|---|---|
| Variable | Edurant + BR N=686 n/N (%) | Efavirenz + BR N=682 n/N (%) | Edurant + BR N=686 n/N (%) | Efavirenz + BR N=682 n/N (%) | ||||||
| Virological Response by Background NRTI | ||||||||||
| tenofovir disoproxil fumarate plus emtricitabine | 459/550 (83.5) | 450/546 (82.4) | 423/550 (76.9) | 422/546 (77.3) | ||||||
| zidovudine plus lamivudine | 88/101 (87.1) | 83/103 (80.6) | 82/101 (81.2) | 79/103 (76.7) | ||||||
| abacavir plus lamivudine | 31/35 (88.6) | 28/33 (84.8) | 27/35 (77.1) | 28/33 (84.8) | |||||
|---|---|---|---|---|---|---|---|---|---|
| Virological Response by Baseline CD4+ Cell Count (cells/mm3) | |||||||||
| <50 | 20/34 (58.8) | 29/36 (80.6) | 19/34 (55.9) | 25/36 (69.4) | |||||
| ≥50 - <200 | 156/194 (80.4) | 143/175 (81.7) | 138/194 (71.1) | 131/175 (74.9) | |||||
| ≥200 - <350 | 272/313 (86.9) | 253/307 (82.4) | 252/313 (80.5) | 244/307 (79.5) | |||||
| ≥350 | 130/144 (90.3) | 136/164 (82.9) | 123/144 (85.4) | 129/164 (78.7) | |||||
| Virological Failure2 by Baseline CD4+ Cell Count (cells/mm3) | |||||||||
| <50 | 6/34 (17.6) | 1/36 (2.8) | 6/34 (17.6) | 4/36 (11.1) | |||||
| ≥50 - <200 | 27/194 (13.9) | 14/175 (8.0) | 37/194 (19.1) | 14/175 (8.0) | |||||
| ≥200 - <350 | 21/313 (6.7) | 14/307 (4.6) | 26/313 (8.3) | 15/307 (4.9) | |||||
| ≥350 | 8/144 (5.6) | 4/164 (2.4) | 10/144 (6.9) | 7/164 (4.3) | |||||
N = number of subjects per treatment group n = number of observations
- 1. Imputations according to the TLOVR algorithm.
- 2. Includes subjects who were rebounder (confirmed viral load ≥50 copies/mL after being responder) or who were never suppressed (no confirmed viral load <50 copies/mL, either ongoing or discontinued due to lack or loss of efficacy).
Trial TMC278-C204
Study TMC278-C204 was a randomized, active-controlled, Phase IIb trial in antiretroviral treatment-naïve HIV-1-infected adult subjects consisting of 2 parts: an initial 96 weeks, partially blinded dose-finding part (Edurant doses blinded) followed by a long-term, open-label part. After Week 96, subjects randomized to one of the 3 doses of Edurant were switched to Edurant 25 mg once daily. Subjects in the control arm received efavirenz 600 mg once daily in addition to a BR in both parts of the study. The BR consisted of 2 investigator-selected N(t)RTIs: zidovudine plus lamivudine or tenofovir disoproxil fumarate plus emtricitabine.
Study TMC278-C204 enrolled 368 HIV-1-infected treatment-naïve adult subjects who had a plasma HIV-1 RNA ≥5000 copies/ml, previously received ≤2 weeks of treatment with an N(t)RTI or protease inhibitor, had no prior use of NNRTIs, and were screened for susceptibility to N(t)RTI and for absence of specific NNRTI RAMs.
At 96 weeks, the proportion of subjects with <50 HIV-1 RNA copies/mL receiving Edurant 25 mg (N = 93) compared to subjects receiving efavirenz (N = 89) was 76% and 71%, respectively. The mean increase from baseline in CD4+ counts was 146 cells/mm3 in subjects receiving Edurant 25 mg and 160 cells/mm3 in subjects receiving efavirenz.
At 240 weeks, 60% (56/93) of subjects who originally received 25 mg once daily achieved HIV RNA <50 copies/mL compared to 57% (51/89) of subjects in the control group.
Treatment-Naïve Pediatric Patients (12 years to less than 18 years of age)
Trial TMC278-C213
The pharmacokinetics, safety, tolerability and efficacy of Edurant 25 mg once daily, in combination with an investigator-selected background regimen (BR) containing two NRTIs, was evaluated in trial TMC278-C213, a single-arm, open-label Phase II trial in antiretroviral treatment-naive HIV-1 infected pediatric subjects 12 to less than 18 years of age and weighing at least 32 kg. This analysis included 36 patients who had completed at least 48 weeks of treatment or discontinued earlier. The 36 subjects had a median age of 14.5 years (range: 12 to 17 years), and were 55.6% female, 88.9% Black and 11.1% Asian.
In the efficacy analysis, most subjects (75%; 28/36) had baseline HIV RNA <100,000 copies/mL. For these 28 subjects, the median baseline plasma HIV-1 RNA was 44,250 (range: 2,060-92,600 copies/mL) and the median baseline CD4+ cell count was 445.5 cells/mm3 (range: 123 to 983 cells/mm3).
Among the subjects who had baseline HIV RNA ≤100,000, the proportion with HIV-1 RNA <50 copies/mL at Week 48 (TLOVR) was 79% (22/28), versus 50.0% (4/8) in those with >100,000 copies/mL. The proportion of virologic failures among subjects with a baseline viral load ≤100,000 copies/mL was 17.9% (5/28), versus 37.5% (3/8) in those with >100,000 copies/mL. One subject discontinued due to an adverse event and one subject discontinued due to reasons other than an adverse event or virological failure. At Week 48, the mean increase in CD4+ cell count from baseline was 201.2 cells/mm3.
15 MICROBIOLOGY
Antiviral Activity In Vitro
Rilpivirine exhibited activity against laboratory strains of wild-type HIV-1 in an acutely infected T-cell line with a median EC50 value for HIV-1/IIIB of 0.73 nM (0.27 ng/mL).
Rilpivirine also demonstrated antiviral activity against a broad panel of HIV-1 group M (subtype A, B, C, D, F, G, H) primary isolates with EC50 values ranging from 0.07 to 1.01 nM (0.03 to 0.37 ng/mL) and group O primary isolates with EC50 values ranging from 2.88 to 8.45 nM (1.06 to 3.10 ng/mL).
Rilpivirine showed additive antiviral activity in combination with the N(t)RTIs abacavir, didanosine, emtricitabine, stavudine and tenofovir; the PIs amprenavir, atazanavir, darunavir, indinavir, lopinavir, nelfinavir, ritonavir, saquinavir and tipranavir; the NNRTIs efavirenz, etravirine and nevirapine; the fusion inhibitor enfuvirtide; and the entry inhibitor maraviroc. Rilpivirine shows additive to synergistic antiviral activity in combination with the NRTIs lamivudine and zidovudine, and the integrase inhibitor raltegravir.
Resistance
Resistance in Vitro
Rilpivirine-resistant strains were selected in cell culture starting from wild-type HIV-1 of different origins and subtypes as well as NNRTI resistant HIV-1. The most commonly observed amino acid substitutions that emerged included: L100I, K101E, V108I, E138K, V179F, Y181C, H221Y, F227C and M230I.
Resistance to rilpivirine was determined as a fold change in EC50 value (FC) above the biological cut-off (BCO) of the assay.
Resistance in Treatment-Naïve Adult Subjects
Considering all of the available in vitro and in vivo data, the following amino acid substitutions, when present at baseline, are likely to decrease the antiviral activity of rilpivirine: K101E, K101P, E138A, E138G, E138K, E138R, E138Q, V179L, Y181C, Y181I, Y181V, Y188L, H221Y, F227C, M230I, and M230L.
In the pooled analysis from two Phase III trials, the emergence of resistance among subjects was greater in the Edurant arm as compared to the control (efavirenz) arm at Week 48 (10.6%, 5.3%, respectively) and at Week 96 (14%, 7.6% respectively). Fewer virologic failures due to resistance occurred between Week 48 and Week 96 in each of the treatment arms (3.2% and 2.3% in the rilpivirine and control arms, respectively).
Most common emergent NNRTI substitutions in rilpivirine virologic failures at Week 96 included V90I, K101E/P, E138K/G/Q, V179I/L, Y181I/C, V189I, H221Y, F227C/L and M230L. The E138K substitution emerged most frequently during rilpivirine treatment at Week 48 and Week 96, commonly in combination with the M184I mutation. The most common mutations were the same in the Week 48 and Week 96 analyses.
In the Week 96 pooled analysis of the two Phase III trials, of the 35 subjects with virologic failure on Edurant and with phenotypic resistance to rilpivirine, 35 (100%) lost susceptibility to lamivudine/emtricitabine. Of the 17 subjects with virologic failure on efavirenz (control) and with phenotypic resistance to efavirenz, 6 (35%) lost susceptibility to lamivudine/emtricitabine. These data were similar to those obtained in the Week 48 pooled analyses.
Cross-resistance
Site-Directed NNRTI Mutant Virus
In a panel of 67 HIV-1 recombinant laboratory strains with one amino acid substitution at RT positions associated with NNRTI resistance, including the most commonly found K103N and Y181C, rilpivirine showed antiviral activity against 64 (96%) of these strains. The single amino acid substitutions associated with a loss of susceptibility to rilpivirine were: K101P, Y181I and Y181V. The K103N substitution did not show reduced susceptibility to rilpivirine by itself, but the combination of K103N and L100I resulted in a 7-fold reduced susceptibility to rilpivirine.
Recombinant Clinical Isolates
Rilpivirine retained sensitivity (FC≤BCO) against 62% of 4786 HIV-1 recombinant clinical isolates resistant to efavirenz and/or nevirapine. Clinical isolates resistant to rilpivirine (FC>BCO) were usually also resistant to etravirine.
Cross-Resistance in Treatment-Naïve Adult Subjects
In the Week 48 pooled analysis of the two Phase III trials, of the 62 subjects with virologic failure on Edurant for whom phenotypic resistance data was available, 31 (50%) lost susceptibility to rilpivirine and within that subset 28 (90%) were resistant to etravirine, 27 (87%) to efavirenz, and 14 (45%) to nevirapine. Of the 28 subjects with virologic failure on efavirenz (control) for whom phenotypic resistance data was available, 12 (43%) lost susceptibility to efavirenz and within that subset none were resistant to etravirine or to rilpivirine, and 12 (100%) to nevirapine.
In the Week 96 pooled analysis of the two Phase III trials, of the 81 subjects with virologic failure on Edurant for whom phenotypic resistance data was available, 35 (43%) lost susceptibility to rilpivirine and within that subset 32 (91%) were resistant to etravirine, 30 (86%) to efavirenz, and 16 (45%) to nevirapine. Of the 41 subjects with virologic failure on efavirenz (control) for whom phenotypic resistance data was available, 17 (41%) lost susceptibility to efavirenz and within that subset 1 (6%) were resistant to etravirine, none to rilpivirine, and 15 (88%) to nevirapine.
In the week 96 pooled analyses, among virologic failures in the Edurant arm with baseline viral load ≤100,000 copies/mL and with resistance to rilpivirine, there were fewer patients with phenotypic cross-resistance than among those in the Edurant arm with baseline viral load >100,000 copies/mL. 3, 4 and 1 rilpivirine virologic failures with baseline viral load ≤100,000 copies/mL and with resistance to rilpivirine (N = 5) had cross-resistance to efavirenz, etravirine and nevirapine, respectively, compared to 27, 28, and 15 rilpivirine virologic failures with baseline viral load >100,000 copies/mL (N = 30), respectively.
16 NON-CLINICAL TOXICOLOGY
General Toxicology: Animal toxicology studies have been conducted with rilpivirine in mice, rats, rabbits, dogs and cynomolgus monkeys. The target organs and systems of toxicity were the adrenal cortex and the associated steroid biosynthesis (mouse, rat, dog, cynomolgus monkey), the reproductive organs (female mouse, male and female dog), the liver (mouse, rat, dog), the thyroid and pituitary gland (rat), the kidney (mouse, dog), the hematopoietic system (mouse, rat, dog), and the coagulation system (rat).
Carcinogenicity: Rilpivirine was evaluated for carcinogenic potential by oral gavage administration to mice and rats up to 104 weeks. Daily doses of 20, 60 and 160 mg/kg/day were administered to mice, and doses of 40, 200, 500 and 1500 mg/kg/day were administered to rats. An increase in the incidences of hepatocellular adenomas and carcinomas was observed in both mice and rats. An increase in the incidences of follicular cell adenomas and/or carcinomas in the thyroid gland was observed in rats. Administration of rilpivirine did not cause a statistically significant increase in the incidence of any other benign or malignant neoplasm in mice or rats. The observed hepatocellular findings in mice and rats may be rodent-specific, associated with liver enzyme induction. The follicular cell findings may be rat-specific, associated with increased clearance of thyroxine. At the lowest tested doses in the carcinogenicity studies, the systemic exposures (based on AUC) to rilpivirine were 21-fold (mice) and 3-fold (rats), relative to those observed in humans at the recommended dose (25 mg q.d.).
Genotoxicity: Rilpivirine has tested negative in the in vitro Ames reverse mutation assay and in vitro clastogenicity mouse lymphoma assay, tested in the absence and presence of a metabolic activation system. Rilpivirine did not induce chromosomal damage in the in vivo micronucleus test in mice.
Reproductive and Developmental Toxicology: In a study conducted in rats, there were no effects on mating or fertility with rilpivirine up to 400 mg/kg/day, a dose of rilpivirine that showed maternal toxicity. This dose is associated with an exposure that is approximately 40 times higher than the exposure in humans at the recommended dose of 25 mg once daily. Studies in animals have shown no evidence of relevant embryonic or fetal toxicity or an effect on reproductive function at exposures relevant for human administration.
There was no teratogenicity with rilpivirine in rats and rabbits. The exposures at the embryo fetal No Observed Adverse Effects Levels (NOAELs) in rats and rabbits were respectively 15 and 70 times higher than the exposure in humans at the recommended dose of 25 mg once daily. In a pre- and postnatal development assessment in rats, rilpivirine had no effect on development of offspring during lactation or post weaning when the mothers were dosed up to 400 mg/kg/day.
Impairment of Fertility
No human data on the effect of rilpivirine on fertility are available. In a study conducted in rats, there were no effects on mating or fertility with rilpivirine up to 400 mg/kg/day, a dose of rilpivirine that showed maternal toxicity. This dose is associated with an exposure that is approximately 40 times higher than the exposure in humans at the recommended dose of 25 mg once daily.