


Product Monograph - Intelence
RECENT MAJOR LABEL CHANGES
| 1 Indications | 03/2024 |
|---|---|
| 1 Indications, 1.1 Pediatrics | 03/2024 |
| 4 Dosage and Administration, 4.2 Recommended Dose and Dosage Adjustment | 03/2024 |
| 4 Dosage and Administration, 4.4 Administration | 10/2022 |
TABLE OF CONTENTS
Sections or subsections that are not applicable at the time of authorization are not listed.
RECENT MAJOR LABEL CHANGES ......................................................................................... 2
TABLE OF CONTENTS ............................................................................................................... 2
PART I: HEALTH PROFESSIONAL INFORMATION .................................................................. 4
1 INDICATIONS ................................................................................................................... 4
1.1 Pediatrics .......................................................................................................... 4
1.2 Geriatrics ........................................................................................................... 4
2 CONTRAINDICATIONS ................................................................................................... 4
4 DOSAGE AND ADMINISTRATION .................................................................................. 5
4.1 Dosing Considerations ...................................................................................... 5
4.2 Recommended Dose and Dosage Adjustment ................................................. 5
4.4 Administration ................................................................................................... 6
4.5 Missed Dose ..................................................................................................... 6
5 OVERDOSAGE ................................................................................................................ 6
6 DOSAGE FORMS, STRENGTHS, COMPOSITION AND PACKAGING ......................... 7
7 WARNINGS AND PRECAUTIONS .................................................................................. 7
7.1 Special Populations ........................................................................................... 9
7.1.1 Pregnant Women ...................................................................................... 9
7.1.2 Breast-feeding ......................................................................................... 10
7.1.3 Pediatrics ................................................................................................ 10
7.1.4 Geriatrics ................................................................................................. 10
8 ADVERSE REACTIONS ................................................................................................. 10
8.1 Adverse Reaction Overview ............................................................................ 10
8.2 Clinical Trial Adverse Reactions ..................................................................... 11
8.2.1 Clinical Trial Adverse Reactions - Pediatrics .......................................... 13
8.3 Less Common Clinical Trial Adverse Reactions ............................................. 13
8.4 Abnormal Laboratory Findings: Hematologic, Clinical Chemistry and Other Quantitative Data ............................................................................................................ 14
8.5 Post-Market Adverse Reactions ...................................................................... 15
9 DRUG INTERACTIONS .................................................................................................. 16
9.2 Drug Interactions Overview ............................................................................. 16
9.4 Drug-Drug Interactions .................................................................................... 16
9.5 Drug-Food Interactions ................................................................................... 28
9.6 Drug-Herb Interactions .................................................................................... 28
9.7 Drug-Laboratory Test Interactions .................................................................. 28
10 CLINICAL PHARMACOLOGY ....................................................................................... 28
10.1 Mechanism of Action ....................................................................................... 28
10.3 Pharmacokinetics ............................................................................................ 29
11 STORAGE, STABILITY AND DISPOSAL ...................................................................... 33
12 SPECIAL HANDLING INSTRUCTIONS ......................................................................... 33
PART II: SCIENTIFIC INFORMATION ....................................................................................... 34
13 PHARMACEUTICAL INFORMATION ............................................................................ 34
14 CLINICAL TRIALS ......................................................................................................... 34
14.1 Clinical Trials by Indication .............................................................................. 34
Treatment-Experienced Adult Patients ........................................................... 34
Treatment-Experienced Pediatric Patients ...................................................... 39
14.2 Comparative Bioavailability Studies ................................................................ 39
15 MICROBIOLOGY ............................................................................................................ 40
16 NON-CLINICAL TOXICOLOGY ..................................................................................... 43
PATIENT MEDICATION INFORMATION .................................................................................. 45
PART I: HEALTH PROFESSIONAL INFORMATION
1 INDICATIONS
INTELENCE® (etravirine), in combination with other antiretroviral agents, is indicated for:
- the treatment of human immunodeficiency virus type 1 (HIV-1) infection in treatment-experienced adult and pediatric (from 6 to <18 years of age and weighing ≥30 kg) patients who have failed prior therapy and have HIV-1 strains resistant to multiple antiretroviral agents, including NNRTIs (see 4 DOSAGE AND ADMINISTRATION).
The adult indication is based on safety and efficacy data at 48 weeks from two Phase III, double-blinded, placebo-controlled trials in treatment-experienced patients who had a least one NNRTI resistance-associated mutation and multiple primary protease inhibitor mutations (see 14 CLINICAL TRIALS for description of studies).
1.1 Pediatrics
Pediatrics (<6 years of age)
The safety and efficacy of Intelence in pediatric patients <6 years of age have not been established. Treatment with Intelence is not indicated for pediatric patients younger than 6 (see 7 WARNINGS AND PRECAUTIONS and 10.3 Pharmacokinetics)
Pediatrics (from 6 to <18 years of age)
Intelence, in combination with other antiretroviral agents, is indicated for the treatment of HIV-1 infection in antiretroviral treatment-experienced pediatric patients 6 years to <18 years of age and weighing ≥30 kg, including those with NNRTI resistance.
This indication is based on 24-week analyses of a single-arm, on-going Phase II trial evaluating safety, PK, and antiretroviral activity in Intelence in antiretroviral treatment-experienced pediatric subjects 6 years to less than 18 years of age. The results of 48 weeks analysis were similar to those of 24 weeks (see 7 WARNINGS AND PRECAUTIONS, 4 DOSAGE AND ADMINISTRATION, and 10 CLINICAL PHARMACOLOGY).
1.2 Geriatrics
Geriatrics (>65 years of age)
Clinical studies of Intelence did not include sufficient numbers of subjects aged 65 and over to determine whether they respond differently from younger subjects. In general, caution should be exercised when administering Intelence in elderly patients, reflecting the greater frequency of decreased hepatic, renal or cardiac function, concomitant disease or other drug therapy (see 7 WARNINGS AND PRECAUTIONS, 4 DOSAGE AND ADMINISTRATION, and 10 CLINICAL PHARMACOLOGY).
2 CONTRAINDICATIONS
- Co-administration of Intelence is contraindicated with the combination ombitasvir/paritaprevir/ritonavir and with drugs containing dasabuvir (see 9 DRUG INTERACTIONS)
- Intelence (etravirine) is contraindicated in patients who are hypersensitive to etravirine or to any ingredient in the formulation or component of the container. For a complete listing, see 6 DOSAGE FORMS, STRENGTHS, COMPOSITION AND PACKAGING.
4 DOSAGE AND ADMINISTRATION
4.1 Dosing Considerations
The following points should be considered when initiating therapy with Intelence:
- Do not use Intelence with only N[t]RTIs in the setting of previous NNRTI failure. This is based on an analysis of an exploratory Phase 2 clinical trial in patients who had experienced virologic failure on an NNRTI- and N[t]RTI-containing regimen (See 14 CLINICAL TRIALS for Description of Studies).
- The use of other active antiretroviral agents with Intelence is associated with an increased likelihood of treatment response.
- Treatment history and, when available, resistance testing, should guide the use of Intelence.
- The safety and efficacy of Intelence have not been established in treatment-naive adult/pediatric patients.
- Intelence must always be given in combination with other antiretroviral medicinal products.
- It is recommended that the dosage of Intelence be taken following a meal. The type of food does not affect the exposure to etravirine.
- Patients should be instructed to swallow the tablet(s) whole with a liquid such as water (see 4.4 Administration).
4.2 Recommended Dose and Dosage Adjustment
Adults
The recommended oral dose of Intelence tablets is 200 mg (one 200 mg tablet or two 100 mg tablets) taken twice daily (b.i.d.) following a meal (see 10.3 Pharmacokinetics).
Geriatric Patients
In general, caution should be exercised in the administration of Intelence in elderly patients, reflecting the greater frequency of decreased hepatic, renal or cardiac function, concomitant disease or other drug therapy (see 1 INDICATIONS, 7 WARNINGS AND PRECAUTIONS and 10.3 Pharmacokinetics).
Pediatric Patients
Treatment-Experienced Pediatric Patients (from 6 to <18 years of age)
The recommended dose of Intelence for pediatric patients (6 years to <18 years of age and weighing at least 30 kg) is 200 mg (one 200 mg tablet or two 100 mg tablets) taken twice daily (b.i.d.). Intelence tablet(s) should be taken orally, following a meal.
Children (<6 years of age)
The safety and efficacy of Intelence in pediatric patients <6 years of age have not yet been established. Treatment with Intelence is not recommended in children younger than 6 (see 1 INDICATIONS, 7 WARNINGS AND PRECAUTIONS and 10.3 Pharmacokinetics).
Pregnancy
No dose adjustment is required during pregnancy and postpartum. Given the increased etravirine exposure during pregnancy, caution should be applied for those pregnant patients that require concomitant medications or have comorbidities that may further increase etravirine exposure.
Hepatic Impairment
No dose adjustment is required in patients with mild or moderate hepatic impairment.
The pharmacokinetics of Intelence has not been studied in patients with severe hepatic impairment (see 7 WARNINGS AND PRECAUTIONS, Hepatic/Biliary/Pancreatic, and 10.3 Pharmacokinetics, Special Populations and Conditions, Hepatic insufficiency).
Renal Impairment
No dose adjustment is required in patients with renal impairment (see 7 WARNINGS AND PRECAUTIONS, Renal and 10.3 Pharmacokinetics, Special Populations and Conditions, Renal Insufficiency).
4.4 Administration
Patients should be instructed to swallow the Intelence tablet(s) whole with a liquid such as water. Patients who are unable to swallow the Intelence tablet(s) whole may disperse the tablet(s) in a glass of water. The patient should be instructed to do the following:
- place the tablet(s) in 5 ml (1 teaspoon) of water, or at least enough liquid to cover the medication,
- stir well for about 1 minute until the water looks milky,
- if desired, add up to 30 mL (2 tablespoons) more water or alternatively orange juice or milk (patients should not place the tablets in orange juice or milk without first adding water),
- drink it immediately,
- rinse the glass several times with water, orange juice, or milk and completely swallow the rinse each time to make sure the patient takes the entire dose.
The use of grapefruit juice, warm liquids (>40°C) or carbonated beverages should be avoided.
In case of any doubt that a child will take the entire dose of the tablet(s) dispersed in water, treatment with another antiretroviral product needs to be considered. For children who cannot swallow the tablet(s) whole, dispersion of the tablet(s) in water should only be considered if the child is likely to take the entire dose. The importance of consuming the entire dose needs to be highlighted to the child and their caregiver to avoid too low exposure and lack of virologic response.
It is recommended that Intelence tablet(s) dispersed in water be taken before other antiretroviral liquids that may need to be taken concomitantly.
4.5 Missed Dose
If the patient misses a dose of Intelence within 6 hours of the time it is usually taken, the patient should be told to take Intelence following a meal as soon as possible, and then take the next dose of Intelence at the regularly scheduled time.
If a patient misses a dose of Intelence by more than 6 hours of the time it is usually taken, the patient should be told not to take the missed dose and simply resume the usual dosing schedule.
5 OVERDOSAGE
There is no specific antidote for overdose with Intelence. Human experience of overdose with Intelence is limited. Treatment of overdose with Intelence consists of general supportive measures including monitoring of vital signs and observation of the clinical status of the patient. Since etravirine is highly protein bound, dialysis is unlikely to be beneficial in significant removal of the active substance.
| For management of a suspected drug overdose, contact your regional poison control centre. |
|---|
6 DOSAGE FORMS, STRENGTHS, COMPOSITION AND PACKAGING
Table 1: Dosage Forms, Strengths, Composition and Packaging
| Route of Administration | Dosage Form / Strength/Composition | Non-medicinal Ingredients |
|---|---|---|
| Oral | tablet, 100 mg | colloidal silicon dioxide, croscarmellose sodium, hypromellose, lactose monohydrate, magnesium stearate, and microcrystalline cellulose. |
| Oral | tablet, 200 mg | colloidal silicon dioxide, croscarmellose sodium, hypromellose, magnesium stearate, microcrystalline cellulose, and silicified microcrystalline cellulose. |
Intelence 100 mg tablets
Intelence tablets are supplied as white to off-white oval tablets containing 100 mg of etravirine.
Each tablet is debossed with “T125” on one side and “100” on the other side. Intelence 100 mg tablets are packaged in bottles in the following configuration: 100 mg tablets—bottles of 120. Each bottle contains 3 desiccant pouches.
Intelence 200 mg tablets
Intelence 200 mg tablets are available as white to off-white, biconvex, oblong tablets containing 200 mg of etravirine.
Each tablet is debossed with “T200” on one side. Intelence 200 mg tablets are packaged in bottles in the following configuration: 200 mg tablets—bottles of 60. Each bottle contains 3 desiccant pouches.
7 WARNINGS AND PRECAUTIONS
General
Patients with hereditary problems of lactose intolerance should not take this medicine.
Carcinogenesis and Mutagenesis
Etravirine was evaluated for carcinogenic potential by oral gavage administration to mice and rats up to 104 weeks. A statistically significant increase in the incidences of hepatocellular adenomas and carcinomas was observed in treated female mice. Administration of etravirine did not cause a statistically significant increase in the incidence of tumors in female or male rats. The relevance of the findings in mice to humans is not known. At the highest tested doses, the systemic exposures (based on AUC) to etravirine were lower than those in humans at the clinical therapeutic dose (200 mg b.i.d) with animal versus human AUC ratios being 0.6 (mice) and between 0.2 and 0.7 (rats) (see 16 NON-CLINICAL TOXICOLOGY, Carcinogenicity and Genotoxicity).
Etravirine tested negative in the in vitro Ames reverse mutation assay, in vitro chromosomal aberration assay in human lymphocyte, and in vitro clastogenicity mouse lymphoma assay, tested in the presence and absence of the metabolic activation system. Etravirine did not induce chromosomal damage in the in vivo micronucleus test in mice (see 16 NON-CLINICAL TOXICOLOGY, Carcinogenicity and Genotoxicity).
Endocrine and Metabolism
Serum Lipids and Blood Glucose
Serum lipids and blood glucose may increase during antiretroviral therapy. Disease control and lifestyle changes may also be contributing factors. Consideration should be given to the measurement of serum lipids and blood glucose. Lipid disorders and blood glucose elevations should be managed as clinically appropriate.
Hepatic/Biliary/Pancreatic
Hepatic Impairment
No dose adjustment is required in patients with mild or moderate hepatic impairment. The pharmacokinetics of Intelence have not been studied in patients with severe hepatic impairment (see 4.2 Recommended Dosage and Dosage Adjustment, Hepatic Impairment and 10 CLINICAL PHARMACOLOGY, Special Populations and Conditions, Hepatic Insufficiency).
Pancreatitis
Pancreatitis has been reported infrequently (<1%) during clinical trials with Intelence. In the placebo-controlled Phase III DUET-1 and DUET-2 trials, the rate of clinical pancreatitis was similar in patients receiving Intelence 4/599 (0.7%) and placebo 2/604 (0.3%). Pancreatitis has been reported in one healthy volunteer (1/1093, 0.09%).
In the DUET trials asymptomatic Grade 3 or 4 increases in serum amylase levels were observed in a similar number of patients treated with Intelence (7.5%) and placebo (7.9%) (see 8 ADVERSE REACTIONS, Laboratory Abnormalities). Grade 3 or 4 elevated lipase levels were reported in 2.7% patients receiving Intelence compared to 1.7% of patients receiving placebo.
Immune
Immune Reconstitution
Immune reconstitution inflammatory syndrome has been reported in patients treated with combination antiretroviral therapy, including Intelence. During the initial phase of treatment, patients responding to antiretroviral therapy may develop an inflammatory response to indolent or residual opportunistic infections (such as MAC, CMV, PCP and TB), which may necessitate further evaluation and treatment.
Autoimmune disorders (such as Graves’ disease, and autoimmune hepatitis, polymyositis and Guillain-Barré syndrome) have also been reported to occur in the setting of immune reconstitution, however, the time to onset is more variable, and can occur many months after initiation of treatment and sometimes there can be an atypical presentation.
Renal
Renal Impairment
Since the renal clearance of etravirine is minimal (<1.2%), a decrease in total body clearance is not expected in patients with renal impairment. No special precautions or dose adjustments are required in patients with renal impairment. As etravirine is highly bound to plasma proteins, it is unlikely that it will be significantly removed by haemodialysis or peritoneal dialysis (see 4 DOSAGE AND ADMINISTRATION and 10 CLINICAL PHARMACOLOGY, Special Populations and Conditions, Renal Insufficiency).
Skin
Severe, potentially life-threatening, and fatal skin reactions have been reported in patients taking Intelence (etravirine). During both clinical development and postmarket, cases of Stevens-Johnson syndrome, toxic epidermal necrolysis and erythema multiforme have been reported. In a postmarketing epidemiologic study in HIV-1 infected children and adolescents receiving Intelence along with other antiretrovirals, Stevens Johnson Syndrome was reported at a higher incidence (1%) than has been reported in adult clinical trials (< 0.1%). Hypersensitivity reactions including DRESS (Drug Rash with Eosinophilia and Systemic Symptoms) have also been reported and were characterized by rash, constitutional findings, and infrequently organ dysfunction, including hepatic failure.
Discontinue Intelence immediately if signs or symptoms of severe skin reactions or hypersensitivity reactions develop (including, but not limited to, severe rash or rash accompanied by fever, general malaise, fatigue, muscle or joint aches, blisters, oral lesions, conjunctivitis, facial edema, hepatitis, eosinophilia). Clinical status including liver transaminases should be monitored and appropriate therapy initiated. Delay in stopping Intelence treatment after the onset of severe rash may result in a life-threatening reaction.
In Phase III clinical trials, Grade 3 and 4 rashes were reported in 1.3% of subjects receiving Intelence compared to 0.2% of placebo subjects. A total of 2% of HIV-1-infected patients receiving Intelence discontinued from Phase III trials due to rash. Most frequently, rash was mild to moderate, occurred in the second week of therapy and was infrequent after week 4. Rash was mostly self-limiting and generally resolved within 1 to 2 weeks on continued therapy. The incidence of rash was higher in females (see 8 ADVERSE REACTIONS).
7.1 Special Populations
7.1.1 Pregnant Women
There are no adequate and well-controlled studies with etravirine in pregnant women.
Studies in animals have not shown evidence of developmental toxicity or effect on reproductive function and fertility (see 16 NON-CLINICAL TOXICOLOGY, Reproductive and Developmental Toxicity).
Intelence (200 mg b.i.d.), was evaluated in combination with other antiretroviral agents in an open-label study of 15 pregnant women during the second and third trimesters of pregnancy and postpartum. Etravirine pharmacokinetic data are available for 13 women in the second trimester, 10 women in the third trimester and 10 women postpartum. The exposure to total etravirine was generally higher during pregnancy compared with postpartum, and less so for unbound etravirine exposure. Given the increased etravirine exposure during pregnancy, caution should be applied for those pregnant patients that require concomitant medications or have comorbidities that may further increase etravirine exposure (see 10 CLINICAL PHARMACOLOGY, Special Populations and Conditions, Pregnancy and Postpartum). There were no relevant clinical findings in the mothers or in the newborns in this trial.
Intelence should be used during pregnancy only if the potential benefit justifies the potential risk.
Antiretroviral Pregnancy Registry: To monitor maternal-fetal outcomes of pregnant women exposed to Intelence, an Antiretroviral Pregnancy Registry has been established. Physicians are encouraged to register patients by calling 1-800-258-4263.
7.1.2 Breast-feeding
Etravirine is excreted in human breast milk. Because of both the potential for HIV transmission and the potential for adverse events in nursing infants, mothers should be instructed not to breast-feed if they are receiving Intelence.
7.1.3 Pediatrics
The safety assessment in children and adolescents is based on the Week 24 analysis of the single arm, Phase II PIANO trial in which 101 antiretroviral treatment-experienced HIV-1 infected pediatric subjects 6 years to less than 18 years of age and weighing at least 16 kg (35.2 lbs), received Intelence in combination with other antiretroviral agents (see 8 ADVERSE REACTIONS).
The safety and effectiveness of Intelence in pediatric patients less than 6 years of age or in treatment-naive patients have not been established.
7.1.4 Geriatrics
There were insufficient numbers of subjects aged 65 and over in the clinical studies to determine whether they respond differently from younger subjects. In general, caution should be exercised when administering Intelence in elderly patients, reflecting the greater frequency of decreased hepatic, renal or cardiac function, concomitant disease or other drug therapy.
8 ADVERSE REACTIONS
8.1 Adverse Reaction Overview
The safety assessment is based on all data from 1203 patients in the ongoing Phase III placebo-controlled trials in antiretroviral treatment-experienced HIV-1-infected adult patients [DUET-1 (TMC125-C206) and DUET-2 (TMC125-C216)], 599 of whom received Intelence (etravirine), 200 mg b.i.d. In these pooled trials, the median exposure for subjects in the Intelence arm and placebo arm was 52.3 and 51.0 weeks, respectively.
In total, 79.3% and 73.0% of the adult subjects experienced adverse drug reactions (ADRs; i.e., adverse events considered related to Intelence) with Intelence and placebo, respectively. The majority of the ADRs reported during treatment with Intelence were Grade 1 to 2 in severity. Grade 3 or 4 ADRs were reported in 22.2% and 17.2% of the Intelence- and placebo-treated subjects. The most commonly reported Grade 3 or 4 ADRs were hypertriglyceridemia (4.2% in the Intelence arm and 2.3% in the placebo arm), hypercholesterolemia (2.2% in the Intelence arm and 2.3% in the placebo arm), renal failure (2.0% in the Intelence arm and 1.2% in the placebo arm) and anemia (1.7% in the Intelence arm and 1.3% in the placebo arm). ADRs were reported as SAEs in 6.8% and 8.3% of subjects treated with Intelence and placebo, respectively. ADRs that led to permanent discontinuation of the investigational medication were reported in 5.2% of the Intelence-treated subjects and in 2.6% of the placebo-treated subjects. The most commonly reported ADRs (any grade) with Intelence identified from the pooled DUET trials were rash (any type), reported by 19.2% of Intelence-treated subjects and by 10.9% of placebo-treated subjects, diarrhea (18.0% and 23.5%), and nausea (14.9% and 12.8%).
8.2 Clinical Trial Adverse Reactions
Clinical trials are conducted under very specific conditions. The adverse reaction rates observed in the clinical trials; therefore, may not reflect the rates observed in practice and should not be compared to the rates in the clinical trials of another drug. Adverse reaction information from clinical trials may be useful in identifying and approximating rates of adverse drug reactions in real-world use.
Adverse drug reactions (ADRs) of moderate intensity or greater (≥Grade 2) and reported in ≥1% of adult subjects treated with Intelence (200 mg b.i.d.) in the DUET-1 and DUET-2 trials are presented in Table 2. Laboratory abnormalities considered ADRs are included in Table 4.
Table 2: Treatment-Emergent Adverse Reactions1 of at Least Moderate Intensity (Grades 2-4) in ≥1% of Adult Subjects in the Intelence Treatment Groups
| System Organ Class, Preferred Term, % | DUET-1 and DUET-2 Trials | ||||||
|---|---|---|---|---|---|---|---|
Intelence + BR N=599 | Placebo + BR N=604 | ||||||
| Blood and Lymphatic System Disorders | |||||||
| Anemia | 4.0% | 3.8% | |||||
| Thrombocytopenia | 1.3% | 1.5% | |||||
| Cardiac Disorders | |||||||
| Myocardial infarction | 1.3% | 0.3% | |||||
| Gastrointestinal Disorders | |||||||
| Diarrhea | 7.0% | 11.3% | |||||
| Nausea | 5.2% | 4.8% | |||||
| Abdominal pain | 3.5% | 3.1% | |||||
| Vomiting | 2.8% | 2.8% | |||||
| Gastroesophageal reflux disease | 1.8% | 1.0% | |||||
| Flatulence | 1.5% | 1.0% | |||||
| Gastritis | 1.5% | 1.0% | |||||
| General Disorders and Administration Site Conditions | |||||||
| Fatigue | 3.5% | 4.6% | |||||
| Metabolism and Nutrition Disorders | |||||||
| Hypertriglyceridemia | 6.3% | 4.3% | |||||
| Hypercholesterolemia | 4.3% | 3.6% | |||||
| Hyperlipidemia | 2.5% | 1.3% | |||||
| Hyperglycemia | 1.5% | 0.7% | |||||
| System Organ Class, Preferred Term, % | DUET-1 and DUET-2 Trials | ||||||
|---|---|---|---|---|---|---|---|
Intelence + BR N=599 | Placebo + BR N=604 | ||||||
| Diabetes mellitus | 1.3% | 0.2% | |||||
| Nervous System Disorders | |||||||
| Peripheral neuropathy | 3.8% | 2.0% | |||||
| Headache | 3.0% | 4.5% | |||||
| Psychiatric Disorders | |||||||
| Insomnia | 2.7% | 2.8% | |||||
| Anxiety | 1.7% | 2.6% | |||||
| Renal and Urinary Disorders | |||||||
| Renal failure | 2.7% | 2.0% | |||||
| Skin and Subcutaneous Tissue Disorders | |||||||
| Rash | 10.0% | 3.5% | |||||
| Lipohypertrophy | 1.0% | 0.3% | |||||
| Night sweats | 1.0% | 1.0% | |||||
| Vascular Disorders | |||||||
| Hypertension | 3.2% | 2.5% | |||||
N = total number of subjects per treatment group
BR = background regimen
- 1. Includes adverse reactions at least possibly, probably, or very likely related to the drug
Skin Rash
The most frequently reported adverse drug reaction of at least Grade 2 in severity in the Phase III studies was rash (10%). Stevens-Johnson syndrome, severe hypersensitivity reaction, and erythema multiforme were reported in <0.1% of adult subjects during clinical development with Intelence. A total of 2% of HIV-1-infected subjects receiving Intelence discontinued from Phase III trials due to rash. In general, rash was mild to moderate, macular to maculopapular or erythematous, occurred primarily in the second week of therapy and was infrequent after Week 4. Rash generally resolved within 1-2 weeks on continued therapy. In Phase III studies, the incidence of rash was higher in women compared to men in the Intelence arm (reported in 9/60 [15.0%] women versus 51/539 [9.5%] men; discontinuations due to rash were reported in 3/60 [5.0%] women versus 10/539 [1.9%] men). Patients with a history of NNRTI-related rash did not appear to be at increased risk for the development of Intelence-related rash compared to patients without a history of NNRTI-related rash. See Table 3 for a summary of rash events.
Table 3: Rash (Any Type) – Week 48 DUET Analysis
| Rash Summary, n (%) | Placebo N=604 | Pooled DUET Trials N=599 |
|---|---|---|
| Rash (any type) | 66 (10.9) | 115 (19.2) |
| Grade 1 | 46 (7.6) | 61 (10.2) |
| Grade 2 | 21 (3.5) | 52 (8.7) |
| Grade 3 | 0 | 8 (1.3) |
| Onset in days, median | 50.0 | 14.0 |
| Duration in days, median | 26.0 | 15.0 |
| Leading to permanent stop | 0 | 13 (2.2) |
| Rash Summary, n (%) | Placebo N=604 | Pooled DUET Trials N=599 |
|---|---|---|
| Vesicular Rash | 1 (0.2) | 0 |
N = number of subjects, n = number of subjects with observations
8.2.1 Clinical Trial Adverse Reactions - Pediatrics
Clinical Trial Experience in Pediatric Patients (6 years to <18 years)
The safety assessment in children and adolescents is based on the Week 24 analysis of the single arm, Phase II PIANO trial (TMC125-C213) in which 101 antiretroviral treatment-experienced HIV-1 infected pediatric subjects 6 years to <18 years of age and weighing at least 16 kg (35.2 lbs), received Intelence in combination with other antiretroviral agents (see 14 CLINICAL TRIALS). The frequency, type and severity of adverse drug reactions in pediatric subjects were comparable to those observed in adults. Adverse Reactions with at least Grade 2 in severity and occurred more than 2% in pediatric subjects were rash (14.9%), diarrhea (5.9%), vomiting (4.0%), headache (4.0%), bronchospasm (3.0%), and hypercholesterolemia (3.0%). Rash was reported more frequently in female subjects than in male subjects (rash ≥Grade 2 was reported in 13/64 [20.3%] females versus 2/37 [5.4%] males; discontinuations due to rash were reported in 4/64 [6.3%] females versus 0/37 [0%] males). Rash was mostly mild to moderate and self-limiting, of macular/papular type, and occurred in the second week of therapy. Rash was generally resolved within 1 week on continued therapy. Rash including serious (Grade 3 or 4) events and discontinuations were more frequently observed in female subjects compared to male subjects. The safety profile for subjects who completed 48 weeks of treatment was similar to the safety profile of subjects who completed 24 weeks of treatment.
8.3 Less Common Clinical Trial Adverse Reactions
Treatment-emergent adverse drug reactions in the DUET-1 and DUET-2 trials (n=599) occurring in less than 1% of adult patients receiving Intelence (200 mg b.i.d.), and of at least moderate intensity (≥Grade 2) are listed below by body system:
Cardiac disorders: angina pectoris, atrial fibrillation
Ear and labyrinth disorders: vertigo
Eye disorders: blurred vision
Gastrointestinal disorders: abdominal distension, constipation, dry mouth, hematemesis, pancreatitis, retching, stomatitis
General disorders and administration site conditions: sluggishness
Hepatobiliary disorders: cytolytic hepatitis, hepatic steatosis, hepatitis, hepatomegaly
Immune system disorders: drug hypersensitivity, immune reconstitution inflammatory syndrome
Metabolism and nutrition disorders: anorexia, dyslipidemia
Nervous system disorders: convulsion, disturbance in attention, hypoesthesia, syncope, amnesia, hypersomnia, paraesthesia, somnolence, tremor
Psychiatric disorders: abnormal dreams, confusional state, disorientation, nervousness, nightmares, sleep disorders
Reproductive system and breast disorders: gynecomastia
Respiratory, thoracic and mediastinal disorders: bronchospasm, exertional dyspnea
Skin and subcutaneous tissue disorders: dry skin, hyperhidrosis, prurigo, swelling face
Additional ADRs observed in other trials occurring in less than 1% of patients receiving Intelence (200 mg b.i.d.), and of at least moderate intensity (≥ Grade 2) are listed below by body system:
Metabolism and nutrition disorders: acquired lipodystrophy
Nervous system disorders: haemorrhagic stroke
Skin and subcutaneous tissue disorders: angioneurotic edema, erythema multiforme, Stevens-Johnson Syndrome, toxic epidermal necrolysis
Additional ADRs of at least moderate intensity observed in other trials were acquired lipodystrophy, angioneurotic edema, erythema multiforme and haemorrhagic stroke, each reported in no more than 0.5% of subjects. Stevens-Johnson syndrome has been reported rarely (<0.1%) during clinical development with Intelence.
8.4 Abnormal Laboratory Findings: Hematologic, Clinical Chemistry and Other Quantitative Data
Treatment-emergent clinical laboratory abnormalities (Grade 3 or 4) observed in adult patients and reported in greater than or equal to 2% of Intelence-treated subjects are presented in the table below. All other Grade 3 or 4 abnormal laboratory parameters were observed in less than 2% of the Intelence-treated subjects.
Table 4: Treatment Emergent Grade 3 to 4 Laboratory Abnormalities Reported in ≥2% of Adult Subjects
| Pooled DUET-1 and DUET-2 Trials | |||||
|---|---|---|---|---|---|
Laboratory Parameter Preferred Term, n (%) | Intelence + BR N=599 | Placebo + BR N=604 | |||
| GENERAL BIOCHEMISTRY | |||||
| Pancreatic amylase | 53 (8.9) | 57 (9.4) | |||
| Grade 3 | 44 (7.4) | 51 (8.4) | |||
| Grade 4 | 9 (1.5) | 6 (1.0) | |||
| Creatinine | 12 (2.0) | 10 (1.7) | |||
| Grade 3 | 12 (2.0) | 9 (1.5) | |||
| Grade 4 | 0 (0) | 1 (0.2) | |||
| Lipase | 20 (3.4) | 16 (2.6) | |||
| Grade 3 | 12 (2.0) | 13 (2.2) | |||
| Grade 4 | 8 (1.3) | 3 (0.5) | |||
| GENERAL HEMATOLOGY | |||||
| White blood cell count | 12 (2.0) | 26 (4.3) | |||
| Grade 3 | 6 (1.0) | 22 (3.6) | |||
| Pooled DUET-1 and DUET-2 Trials | |||||
|---|---|---|---|---|---|
Laboratory Parameter Preferred Term, n (%) | Intelence + BR N=599 | Placebo + BR N=604 | |||
| Grade 4 | 6 (1.0) | 4 (0.7) | |||
| HEMATOLOGY DIFFERENTIAL COUNTS | |||||
| Neutrophils | 30 (5.1) | 45 (7.5) | |||
| Grade 3 | 21 (3.5) | 26 (4.3) | |||
| Grade 4 | 9 (1.5) | 19 (3.1) | |||
| LIPIDS AND GLUCOSE | |||||
| Total cholesterol | 48 (8.1) | 32 (5.3) | |||
| Grade 3 | 48 (8.1) | 32 (5.3) | |||
| Low density lipoprotein | 42 (7.2) | 39 (6.6) | |||
| Grade 3 | 42 (7.2) | 39 (6.6) | |||
| Elevated glucose levels | 21 (3.5) | 14 (2.3) | |||
| Grade 3 | 21 (3.5) | 13 (2.2) | |||
| Grade 4 | 0 (0) | 1 (0.2) | |||
| Triglycerides | 55 (9.2) | 35 (5.8) | |||
| Grade 3 | 34 (5.7) | 24 (4.0) | |||
| Grade 4 | 21 (3.5) | 11 (1.8) | |||
| HEPATIC PARAMETERS | |||||
| Alanine amino transferase | 22 (3.7) | 12 (2.0) | |||
| Grade 3 | 16 (2.7) | 10 (1.7) | |||
| Grade 4 | 6 (1.0) | 2 (0.3) | |||
| Aspartate amino transferase | 19 (3.2) | 12 (2.0) | |||
| Grade 3 | 16 (2.7) | 10 (1.7) | |||
| Grade 4 | 3 (0.5) | 2 (0.3) | |||
BR = Background regimen
Patients Co-infected with Hepatitis B and/or Hepatitis C Virus
In the pooled analysis for DUET-1 and DUET-2, the safety profile in co-infected adult subjects (139) was generally comparable between subjects receiving Intelence and subjects receiving placebo. There was a higher incidence of hepatic and biliary system disorders in co-infected subjects treated with Intelence (12.5% of 72 subjects) compared to co-infected subjects in the placebo group (9.0% of 67 subjects). No specific pattern or type of event was observed.
Among co-infected subjects:
- Grade 3 or 4 elevations in AST developed in 9.7% of subjects in the Intelence arm compared to 6.0% of subjects in the placebo arm;
- Grade 3 or 4 elevations in ALT developed in 11.1% of subjects in the Intelence arm compared to 7.5% of subjects in the placebo arm;
- Grade 3 or 4 elevations in bilirubin developed in 5.7% of subjects in the Intelence arm compared to 1.5% of subjects in the placebo arm.
8.5 Post-Market Adverse Reactions
Immune system disorders: Immune reconstitution inflammatory syndrome, Severe hypersensitivity reactions including DRESS (Drug Rash with Eosinophilia and Systemic Symptoms) with cases of hepatic failure (see 7 WARNINGS AND PRECAUTIONS, Immune).
Skin and subcutaneous tissue disorders: Fatal cases of toxic epidermal necrolysis (see 7 WARNINGS AND PRECAUTIONS, Skin).
Musculoskeletal and connective tissue disorders: Myopathy, Rhabdomyolysis
Post Marketing Studies in Pediatric Patients:
In a pharmacovigilance postmarketing epidemiologic study to define the long-term safety profile of etravirine in HIV-1-infected children and adolescents receiving etravirine with other HIV-1 antiretrovirals (N=182), Stevens-Johnson Syndrome was reported at a higher incidence (1%) than has been reported in adult clinical trials (<0.1%).
9 DRUG INTERACTIONS
9.2 Drug Interactions Overview
Etravirine is metabolized by cytochrome CYP3A4, CYP2C9 and CYP2C19 followed by glucuronidation of the metabolites by uridine diphosphate glucuronosyltransferase (UDPGT). Therefore, co-administration of Intelence with drugs that induce or inhibit CYP3A, CYP2C9, or CYP2C19 may result in altered plasma concentrations of etravirine and alter the therapeutic effect or adverse reaction profile of Intelence.
Etravirine is an inducer of CYP3A4, and an inhibitor of CYP2C9, CYP2C19 and P-glycoprotein. Therefore, co-administration of drugs that are substrates of CYP3A4, CYP2C9, CYP2C19 or that are transported by the P-glycoprotein with Intelence may result in altered plasma concentrations and alter the therapeutic effect or adverse reaction profile of the co-administered drug(s).
9.4 Drug-Drug Interactions
Co-adminitstration of Intelence is contraindicated with the combination ombitasvir/paritaprevir/ritonavir and with drugs containing dasabuvir because decrease in exposure (CYP3A induction by etravirine) may lead to a potential loss of therapeutic activity of ombitasvir/paritaprevir/ritonavir or dasabuvir (see 2 CONTRAINDICATIONS).
Drugs that are not recommended for co-administration with Intelence are included in Table 5. These recommendations are based on either drug interaction studies or predicted interactions due to the expected magnitude of interaction and potential for serious events or loss of efficacy.
Table 5: Drugs That Should Not Be Co-administered With Intelence
| Concomitant Drug Class: Drug Name | Clinical Comment |
|---|---|
| HIV-Antiviral Agents: Non-Nucleoside Reverse Transcriptase Inhibitors (NNRTIs) | |
efavirenz nevirapine delavirdine rilpivirine | Combining two NNRTIs has not been shown to be beneficial. Concomitant use of Intelence with efavirenz or nevirapine may cause a decrease in the plasma concentrations of etravirine and loss of therapeutic effect of Intelence. Intelence and other NNRTIs should not be co-administered. Combining two NNRTIs has not been shown to be beneficial. Intelence and delavirdine or rilpivirine should not be co-administered. |
| Concomitant Drug Class: Drug Name | Clinical Comment |
|---|---|
| HIV-Antiviral Agents: HIV Protease Inhibitors (PIs)—Unboosted (i.e., without co-administration of low-dose ritonavir) | |
| ritonavir | Concomitant use of Intelence with full-dose ritonavir (600 mg b.i.d.) may cause a significant decrease in the plasma concentration of etravirine. This may result in loss of therapeutic effect of Intelence. It is not recommended to co-administer full-dose ritonavir (600 mg b.i.d.) with Intelence. |
atazanavir nelfinavir indinavir | Concomitant use of Intelence without co-administration of low-dose ritonavir may cause a significant alteration in the plasma concentrations of the PI. Intelence should not be co-administered with PIs without low-dose ritonavir. |
| HIV-Antiviral Agents: HIV Protease Inhibitors (PIs)—Boosted (with co-administration of low-dose ritonavir) | |
fosamprenavir/ritonavir tipranavir/ritonavir | An increase of 69% for amprenavir exposure was observed when fosamprenavir/ritonavir was co-administered in the presence of etravirine. Appropriate doses of the combination of Intelence and fosamprenavir/ritonavir have not been established. Intelence and fosamprenavir/ritonavir should not be co-administered. Concomitant use of Intelence with tipranavir/low-dose ritonavir may cause a significant decrease in the plasma concentration of etravirine and loss of therapeutic effect of Intelence. Tipranavir/low-dose ritonavir and Intelence should not be co-administered. |
| HIV-Antiviral Agents: HIV Protease Inhibitiors (PIs) – Boosted (with co-administration of cobicistat) | |
atazanavir/cobicistat darunavir/cobicistat | Co-administration of Intelence with atazanavir/cobicistat or darunavir/cobicistat may decrease plasma concentrations of the PI and/or cobicistat, which may result in loss of therapeutic effect and development of resistance. Co-administration of Intelence with atazanavir/cobicistat or darunavir/cobicistat is not recommended. |
| Hepatitis C Virus (HCV) Direct-Acting Antivirals: | |
elbasvir/grazoprevir simeprevir | Co-administration of Intelence with elbasvir/grazoprevir may decrease elbasvir and grazoprevir concentrations, leading to reduced therapeutic effect of elbasvir/grazoprevir. It is not recommended to co-administer Intelence with elbasvir/grazoprevir. Concomitant use of Intelence with simeprevir may decrease plasma concentrations of simeprevir. It is not recommended to co-administer Intelence with simeprevir. |
| Concomitant Drug Class: Drug Name | Clinical Comment |
|---|---|
Anticonvulsants: carbamazepine phenobarbital phenytoin | Carbamazepine, phenobarbital and phenytoin are inducers of CYP450 enzymes. Intelence should not be used in combination with carbamazepine, phenobarbital, or phenytoin as co-administration may cause significant decreases in etravirine plasma concentrations and loss of therapeutic effect of Intelence. |
Antimycobacterials: rifampin | Rifampin is a potent inducer of CYP450 enzymes. Intelence should not be used in combination with rifampin as co-administration may cause significant decreases in etravirine plasma concentrations and loss of therapeutic effect of Intelence. |
Herbal Products: St. John's Wort (Hypericum perforatum) | Intelence should not be used concomitantly with products containing St. John’s Wort because co-administration may cause significant decreases in etravirine plasma concentrations and loss of therapeutic effect of Intelence. |
Established and other potentially significant drug interactions with Intelence are included in Table 6. These recommendations are based on either drug interaction studies or predicated interactions due to the expected magnitude of interaction and potential for serious events or loss of efficacy.
Table 6: Established and Other Potentially Significant Drug Interactions: Alterations in Dose or Regimen May Be Recommended Based on Drug Interaction Trials or Predicted Interaction
| Concomitant Drug Class: Drug Name | Effect on Concentration of Etravirine or Concomitant Drug | Clinical Comment |
|---|---|---|
| HIV-Antiviral Agents: Nucleoside or Nucleotide Reverse Transcriptase Inhibitors (NRTIs/N[t]RTIs) | ||
| didanosine1 | ↔ etravirine ↔ didanosine | No dose adjustments for Intelence and didanosine are needed when co-administered. As didanosine is administered on an empty stomach, didanosine should be administered one hour before or two hours after Intelence (which should be administered following a meal). |
| tenofovir disoproxil fumarate1 | ↓ etravirine ↔ tenofovir | No dose adjustments for Intelence and tenofovir disoproxil fumarate are needed when co-administered. |
| Other NRTIs: Based on the primarily renal elimination route for other NRTIs (e.g., abacavir, emtricitabine, lamivudine, stavudine, and zidovudine), no drug interactions are expected between these drugs and Intelence. | ||
| HIV-Antiviral Agents: Protease Inhibitors (PIs)—Boosted (with co-administration of low-dose ritonavir) | ||
| Concomitant Drug Class: Drug Name | Effect on Concentration of Etravirine or Concomitant Drug | Clinical Comment |
|---|---|---|
| atazanavir/ritonavir | ↔ etravirine ↓ atazanavir | Concomitant use of Intelence with atazanavir/ritonavir may decrease, in some cases significantly, the Cmin of atazanavir. Caution should be exercised when Intelence is co-administered with atazanavir/ritonavir. Close monitoring for HIV virologic response is recommended. |
| darunavir/ritonavir1 | ↓ etravirine ↔ darunavir | The mean systemic exposure (AUC) of etravirine was reduced by 37% when Intelence was co-administered with darunavir/ritonavir. However, the combination of darunavir/ritonavir and etravirine was used safely and effectively in the Phase III trials, therefore, no dose adjustments for Intelence and darunavir/ritonavir are needed when co-administered. |
| lopinavir/ritonavir (soft gel capsule)1 | ↑ etravirine ↓ lopinavir | The mean systemic exposure (AUC) of etravirine after co-administration of Intelence with lopinavir/ritonavir is anticipated to be about 85% higher than the mean AUC of etravirine observed in the Phase III trials2. The amount of safety data at these increased etravirine exposures is limited, therefore, Intelence and lopinavir/ritonavir should be co-administered with caution. |
| lopinavir/ritonavir (tablet)1 | ↔ lopinavir ↓ etravirine | The mean systemic exposure (AUC) of etravirine was reduced by approximately 35% after co-administration with lopinavir/ritonavir. This reduction is similar to the reduction in the mean systemic exposure of etravirine in the presence of darunavir/ritonavir observed in Phase III trials, therefore Intelence can be co-administered with the tablet formulation of lopinavir/ritonavir without dose adjustments. |
| saquinavir/ritonavir1 | ↓ etravirine ↔ saquinavir | The mean systemic exposure (AUC) of etravirine was reduced by about 33% after co-administration of Intelence and saquinavir/ritonavir. The reduction in the mean systemic exposures of etravirine in the presence of saquinavir/ritonavir is similar to the reduction in mean systemic exposures of etravirine in the presence of darunavir/ritonavir, therefore, no dose adjustments for Intelence and saquinavir/ritonavir are needed when co-administered. |
| HIV-Antiviral Agents: Dual Boosted HIV Protease Inhibitors | ||
| lopinavir/saquinavir/ ritonavir1 | ↔ etravirine ↓ lopinavir ↓ saquinavir | No dose adjustments for Intelence and lopinavir/saquinavir/ritonavir are needed when co-administered. |
| CCR5 Antagonists | ||
| Concomitant Drug Class: Drug Name | Effect on Concentration of Etravirine or Concomitant Drug | Clinical Comment |
|---|---|---|
| maraviroc | ↔ etravirine ↓ maraviroc | Concomitant use of Intelence with maraviroc may cause a significant decrease (53%) in the plasma concentration of maraviroc. When Intelence is co-administered with maraviroc in the absence of a potent CYP3A4 inhibitor (e.g., a boosted PI), the recommended dose of maraviroc is 600 mg b.i.d. No dose adjustment for Intelence is needed. |
maraviroc/darunavir/ ritonavir | ↔ etravirine ↑ maraviroc | When Intelence is co-administered with maraviroc in the presence of a potent CYP3A inhibitor (e.g., a boosted PI), the recommended dose of maraviroc is 150 mg b.i.d. No dose adjustment of Intelence is needed. |
| HIV-Antiviral Agents: Fusion Inhibitors | ||
| enfuvirtide | ↔ etravirine ↔ enfuvirtide | No interaction is expected for either Intelence or enfuvirtide when co-administered. |
| HIV-Antiviral Agents: Integrase Strand Transfer Inhibitors | ||
dolutegravir dolutegravir/darunavir /ritonavir dolutegravir/lopinavir /ritonavir | ↔ etravirine ↓ dolutegravir ↔ etravirine ↓ dolutegravir ↔ etravirine ↔ dolutegravir | Intelence significantly reduced plasma concentrations of dolutegravir. Using cross-study comparisons to historical pharmacokinetic data for Intelence, dolutegravir did not appear to affect the pharmacokinetics of Intelence. The effect of Intelence on dolutegravir plasma concentrations was mitigated by co-administration of darunavir/ritonavir or lopinavir/ritonavir and is expected to be mitigated by atazanavir/ritonavir. Dolutegravir should only be used with Intelence when co-administered with atazanavir/ritonavir, darunavir/ritonavir, or lopinavir/ritonavir. |
| raltegravir1 | ↔ etravirine ↓ raltegravir | No dose adjustment s for Intelence and raltegravir are needed when co-administered. |
| Other Agents | ||
Antiarrhythmics: amiodarone bepridil disopyramide flecainide lidocaine (systemic) mexiletine propafenone quinidine digoxin | ↓ antiarrhythmics ↑ digoxin ↔ etravirine | Concentrations of these antiarrhythmics may be decreased when co-administered with Intelence. Caution is warranted and therapeutic concentration monitoring, if available, is recommended for antiarrhythmics when co-administered with Intelence. No dose adjustments for Intelence and digoxin are needed when co-administered. It is recommended that digoxin levels be monitored when digoxin is combined with Intelence. |
| Concomitant Drug Class: Drug Name | Effect on Concentration of Etravirine or Concomitant Drug | Clinical Comment |
|---|---|---|
Anticoagulants: warfarin | ↑ warfarin | Warfarin concentrations may be affected when co-administered with Intelence. Co-administration of Intelence and warfarin is anticipated to cause an increase in warfarin exposures, while etravirine exposures are not expected to change. It is recommended that the international normalized ratio (INR) be monitored when warfarin is combined with Intelence. |
Anti-infectives: azithromycin clarithromycin1 | ↔ etravirine ↔ azithromycin ↑ etravirine ↓ clarithromycin ↑ 14-OH-clarithromycin | Based on the renal elimination pathway of azithromycin, no drug interactions are expected between azithromycin and Intelence. Clarithromycin exposure was decreased by etravirine; however, concentrations of the active metabolite, 14-hydroxy-clarithromycin, were increased. Because 14-hydroxy-clarithromycin has reduced activity against Mycobacterium avium complex (MAC), overall activity against this pathogen may be altered; therefore, alternatives to clarithromycin, such as azithromycin, should be considered for the treatment of MAC. |
Antimalarials: artemether/lumefantrine | ↔ etravirine ↓ artemether ↓ dihydroartemisinin ↓ lumefantrine | No dose adjustment is needed for Intelence. Caution is warranted when co-administering Intelence and artemether/lumefantrine as it is unknown whether the decrease in exposure of artemether or its active metabolite, dihydroartemisinin, could result in decreased antimalarial efficacy. |
Antifungals: fluconazole | ↔ fluconazole ↑ etravirine ↑ voriconazole | The plasma concentrations of Intelence are increased when co-administered with fluconazole (a potent inhibitor of CYP2C9) or with voriconazole, (a substrate and inhibitor of CYP3A, CYP2C9 and CYP2C19). The mean systemic exposure (AUC) of etravirine after co-administration of Intelence with fluconazole or voriconazole in the absence of a boosted HIV protease inhibitor is anticipated to be about 194% and 114% higher, respectively, as compared to the mean AUC of etravirine observed in Phase III trials2. There is limited safety data on these increased etravirine exposures. Therefore, Intelence and either fluconazole or voriconazole should be co-administered with caution. Dose adjustments for voriconazole may be necessary depending on other co-administered drugs. |
| Concomitant Drug Class: Drug Name | Effect on Concentration of Etravirine or Concomitant Drug | Clinical Comment |
|---|---|---|
Itraconazole posaconazole ketoconazole | ↑ etravirine ↓ itraconazole ↔ posaconazole ↓ ketoconazole | Posaconazole is a potent inhibitor of CYP3A and may increase plasma concentrations of etravirine. Itraconazole and ketoconazole are potent inhibitors as well as substrates of CYP3A. Concomitant systemic use of itraconazole or ketoconazole and Intelence may increase plasma concentrations of etravirine. Simultaneously, plasma concentrations of itraconazole or ketoconazole may be decreased by Intelence. Dose adjustments for itraconazole or ketoconazole may be necessary depending on other co-administered drugs. |
| Antimycobacterials: rifabutin1 | ↓ etravirine ↓ rifabutin ↓ 25-O- desacetylrifabutin | The combination of Intelence and rifabutin should be used with caution due to the risk of decrease in etravirine and rifabutin exposures. If Intelence is co-administered with darunavir/ritonavir, saquinavir/ritonavir or the tablet formulation of lopinavir/ritonavir, then rifabutin should not be co-administered due to the potential for significant reductions in etravirine exposure. |
| Benzodiazepines: diazepam | ↑ diazepam | Concomitant use of Intelence with diazepam may increase plasma concentrations of diazepam. A decrease in diazepam dose may be needed. |
Corticosteroids: dexamethasone (systemic) | ↓ etravirine | Systemic dexamethasone induces CYP3A and can decrease etravirine plasma concentrations. This may result in loss of therapeutic effect of Intelence. Systemic dexamethasone should be used with caution or alternatives should be considered, particularly for long-term use. |
Estrogen-based Contraceptives: ethinylestradiol1 norethindrone1 | ↔ etravirine ↑ ethinylestradiol ↔ norethindrone | No dose adjustments for Intelence and estrogen and/or progesterone based contraceptives are needed when co-administered. |
Hepatitis C Virus (HCV) Direct-Acting Antivirals: daclatasvir ribavirin | ↓ daclatasvir | Co-administration of Intelence with daclatasvir may decrease daclatasvir concentrations. Increase the daclatasvir dose to 90 mg once daily. Based on the renal elimination pathway of ribavirin, no drug interactions are expected between ribavirin and Intelence. |
| Concomitant Drug Class: Drug Name | Effect on Concentration of Etravirine or Concomitant Drug | Clinical Comment |
|---|---|---|
HMG-CoA Reductase Inhibitors: atorvastatin1 | ↔ etravirine ↓ atorvastatin ↑ 2-OH-atorvastatin | Atorvastatin plasma concentrations are decreased 37% and plasma concentrations of the active metabolite, 2-hydroxy-atorvastatin, are increased by 27% when combined with Intelence. Dose adjustment of atorvastatin may be necessary to tailor the clinical response when combined with Intelence. |
fluvastatin lovastatin pravastatin rosuvastatin simvastatin | ↔ etravirine ↑ fluvastatin ↓ lovastatin ↔ pravastatin ↔ rosuvastatin ↓ simvastatin | No interaction between pravastatin and Intelence is expected. Lovastatin, rosuvastatin, and simvastatin are CYP3A substrates and co-administration with Intelence may result in lower plasma concentrations of the HMG-CoA reductase inhibitor. Fluvastatin and rosuvastatin are metabolized by CYP2C9. Co-administration of fluvastatin with Intelence may result in higher plasma concentrations of the HMG-CoA reductase inhibitor. Dose adjustments for fluvastatin may be necessary. No interaction between rosuvastatin and Intelence is expected. |
H2-Receptor Antagonists: ranitidine1 | ↓ etravirine | No dose adjustment of Intelence is needed when co-administered with H2 receptor antagonists. |
Immunosuppressants: cyclosporine sirolimus tacrolimus | ↓ cyclosporine ↓ sirolimus ↓ tacrolimus | Co-administration with systemic immunosuppressants should be done with caution because plasma concentrations of cyclosporine, sirolimus, or tacrolimus may be affected when co-administered with Intelence. |
| Narcotic Analgesics: methadone1 | ↔ etravirine ↔ R(-) methadone ↔ S(+) methadone | Intelence and methadone may be co-administered without dose adjustments, however, clinical monitoring for withdrawal symptoms is recommended as methadone maintenance therapy may need to be adjusted in some patients. |
Phosphodiesterase Type 5 (PDE-5) Inhibitors: sildenafil1 vardenafil tadalafil | ↓ sildenafil ↓ N-desmethyl-sildenafil | Sildenafil plasma concentrations are decreased by 57% and plasma concentrations of the active metabolite, N-desmethyl-sildenafil, are decreased by 41% when combined with Intelence. Concomitant use of PDE-5 inhibitors with Intelence may require dose adjustment of the PDE-5 inhibitor to attain the desired clinical effect. |
Platelet Aggregation Inhibitors: clopidogrel | Activation of clopidogrel to its active metabolite may be decreased when clopidogrel is co-administered with Intelence. Alternatives to clopidogrel should be considered. |
| Concomitant Drug Class: Drug Name | Effect on Concentration of Etravirine or Concomitant Drug | Clinical Comment |
|---|---|---|
Proton Pump Inhibitors: omeprazole1 | ↑ etravirine | No dose adjustment of Intelence is needed when co-administered with proton pump inhibitors. |
Selective Serotonin Reuptake Inhibitors (SSRIs): paroxetine1 | ↔ etravirine ↔ paroxetine | No dose adjustment of Intelence is needed when co-administered with paroxetine. |
↑ = increases, ↓ = decreases, ↔ = no change
- 1. The interaction between Intelence and the drug was evaluated in a clinical trial. All other drug interactions shown are predicted.
- 2. The expected increase in systemic exposure of etravirine when co-administered with either lopinavir/ritonavir tablet (~85%), fluconazole (~194%) or voriconazole (~114%) is theoretical and is based on comparisons of etravirine exposures from drug-drug interaction studies to those in the pivotal Phase III trials (in which darunavir/ritonavir was co-administered as part of the background regimen).
Drug interaction studies were performed with etravirine and other drugs likely to be co-administered and some drugs commonly used as probes for pharmacokinetic interactions. The effects of co-administration of etravirine on the AUC, Cmax, and Cmin values are summarized in Table 7 and Table 8. Different formulations and/or doses were used which led to similar exposures and, therefore, interactions relevant for one formulation are relevant for the other.
Table 7: Drug Interactions: Pharmacokinetic Parameters for Etravirine in the Presence of Co-administered Drugs1
| Co-administered Drug | Dose/Schedule of Co-administered Drug | N | PK | Mean Ratio of Etravirine Pharmacokinetic Parameters 90% CI; No Effect = 1.00 | ||||||||
|---|---|---|---|---|---|---|---|---|---|---|---|---|
| Cmax | AUC | Cmin | ||||||||||
| Co-Administration With Protease Inhibitors (PIs) | ||||||||||||
| atazanavir | 400 mg q.d. | 14 | ↑ | 1.47 (1.36-1.59) | 1.50 (1.41-1.59) | 1.58 (1.46-1.70) | ||||||
atazanavir/ ritonavir3 | 300/100 mg q.d. | 14 | ↑ | 1.30 (1.17-1.44) | 1.30 (1.18-1.44) | 1.26 (1.12-1.42) | ||||||
darunavir/ ritonavir | 600/100 mg b.i.d. | 14 | ↓ | 0.68 (0.57-0.82) | 0.63 (0.54-0.73) | 0.51 (0.44-0.61) | ||||||
fosamprenavir/ ritonavir | 700/100 mg b.i.d. | 8 | ↔ | N.A. | N.A. | N.A. | ||||||
lopinavir/ ritonavir (soft gel capsule) | 400/100 mg b.i.d. | 13 | ↑ | 1.15 (0.94-1.41) | 1.17 (0.96-1.43) | 1.23 (0.98-1.53) | ||||||
lopinavir/ritonavir (tablet) | 400/100 mg b.i.d. | 16 | ↓ | 0.70 (0.64-0.78) | 0.65 (0.59-0.71) | 0.55 (0.49-0.62) | ||||||
| ritonavir | 100 mg single dose | 18 | ↔ | 1.00 (0.89-1.12) | 1.03 (0.91-1.17) | N.A. | ||||||
| ritonavir | 600 mg b.i.d. | 11 | ↓ | 0.68 (0.55-0.85) | 0.54 (0.41-0.73) | N.A. | ||||||
saquinavir/ ritonavir | 1000/100 mg b.i.d. | 14 | ↓ | 0.63 (0.53-0.75) | 0.67 (0.56-0.80) | 0.71 (0.58-0.87) | ||||||
| Co-administered Drug | Dose/Schedule of Co-administered Drug | N | PK | Mean Ratio of Etravirine Pharmacokinetic Parameters 90% CI; No Effect = 1.00 | ||||||||||
|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|
| Cmax | AUC | Cmin | ||||||||||||
tipranavir/ ritonavir | 500/200 mg b.i.d. | 19 | ↓ | 0.29 (0.22-0.40) | 0.24 (0.18-0.33) | 0.18 (0.13-0.25) | ||||||||
| Co-Administration with Dual Boosted Protease Inhibitors (PIs) | ||||||||||||||
lopinavir/ saquinavir/ ritonavir | 400 mg/800-1000 mg/100 mg b.i.d. | 11 | ↔ | N.A. | N.A. | N.A. | ||||||||
| Co-Administration With Nucleoside Reverse Transcriptase Inhibitors (NRTIs) | ||||||||||||||
| didanosine | 400 mg q.d. | 15 | ↔ | 1.16 (1.02-1.32) | 1.11 (0.99-1.25) | 1.05 (0.93-1.18) | ||||||||
| tenofovir disoproxil fumarate | 300 mg q.d. | 23 | ↓ | 0.81 (0.75-0.88) | 0.81 (0.75-0.88) | 0.82 (0.73-0.91) | ||||||||
| Co-Administration With CCR5 Antagonists | ||||||||||||||
| maraviroc | 300 mg b.i.d. | 14 | ↔ | 1.05 (0.97-1.17) | 1.06 (0.99-1.14.) | 1.08 (0.98-1.19) | ||||||||
| Co-Administration With Fusion Inhibitors | ||||||||||||||
| enfuvirtide | 90 mg b.i.d. | 261 | ↔2 | N.A. | N.A. | N.A. | ||||||||
| Co-Administration With Integrase Strand Transfer Inhibitors | ||||||||||||||
| raltegravir | 400 mg b.i.d. | 19 | ↔ | 1.04 (0.97-1.12) | 1.10 (1.03-1.16) | 1.17 (1.10-1.26) | ||||||||
| Co-Administration With Other Drugs | ||||||||||||||
| atorvastatin | 40 mg q.d. | 16 | ↔ | 0.97 (0.93-1.02) | 1.02 (0.97-1.07) | 1.10 (1.02-1.19) | ||||||||
| boceprevir | 800 mg t.i.d. | 20 | ↓ | 0.76 (0.68-0.85) | 0.77 (0.66-0.91) | 0.71 (0.54-0.95) | ||||||||
| clarithromycin | 500 mg b.i.d. | 15 | ↑ | 1.46 (1.38-1.56) | 1.42 (1.34-1.50) | 1.46 (1.36-1.58) | ||||||||
ethinylestradiol/ norethindrone | 0.035 mg q.d./ 1 mg q.d. | 16 | ↔ | N.A. | N.A. | N.A. | ||||||||
| fluconazole | 200 mg q.a.m. | 16 | ↑ | 1.75 (1.60-1.91) | 1.86 (1.73-2.00) | 2.09 (1.90-2.31) | ||||||||
| methadone | Individual dose regimen ranging from 60 to 130 mg/day | 16 | ↔ | N.A. | N.A. | N.A. | ||||||||
| omeprazole | 40 mg q.d. | 18 | ↑ | 1.17 (0.96-1.43) | 1.41 (1.22-1.62) | N.A. | ||||||||
| paroxetine | 20 mg q.d. | 16 | ↔ | 1.05 (0.96-1.15) | 1.01 (0.93-1.10) | 1.07 (0.98-1.17) | ||||||||
| Ranitidine | 150 mg b.i.d. | 18 | ↓ | 0.94 (0.75-1.17) | 0.86 (0.76-0.97) | N.A. | ||||||||
| Rifabutin | 300 mg q.d. | 12 | ↓ | 0.63 (0.53-0.74) | 0.63 (0.54-0.74) | 0.65 (0.56-0.74) | ||||||||
| voriconazole | 200 mg b.i.d. | 16 | ↑ | 1.26 (1.16-1.38) | 1.36 (1.25-1.47) | 1.52 (1.41-1.64) | ||||||||
CI = Confidence Interval; N = maximum number of subjects with data; N.A. = not available; ↑ = increases; ↓ = decreases; ↔ = no change; q.d. = once daily; b.i.d. = twice daily; t.i.d. = three times daily; q.a.m. = once daily in the morning
- 1. In drug-drug interaction studies, different formulations and/or doses of Intelence were used which led to similar exposures, and, therefore, interactions relevant for one formulation are relevant for the other.
- 2. Based on population pharmacokinetic analysis
- 3. The systemic exposure of etravirine when co-administered with atazanavir/ritonavir in HIV infected patients is similar to exposures of etravirine observed in the Phase III trials after co-administration of Intelence and darunavir/ritonavir (as part of the background regimen).
Table 8: Drug Interactions: Pharmacokinetic Parameters for Co-administered Drugs in the Presence of Etravirine1
| Co-administered Drug | Dose/Schedule of Co-administered Drug | N | PK | Mean Ratio of Co-administered Drug Pharmacokinetic Parameters 90% CI; No effect = 1.00 | ||||||||||||
|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|
| Cmax | AUC | Cmin | ||||||||||||||
| Co-Administration With Protease Inhibitors (PIs) | ||||||||||||||||
| atazanavir | 400 mg q.d. | 14 | ↓ | 0.97 (0.73-1.29) | 0.83 (0.63-1.09) | 0.53 (0.38-0.73) | ||||||||||
atazanavir/ ritonavir | 300/100 mg q.d. | 13 | ↓ | 0.97 (0.89-1.05) | 0.86 (0.79-0.93) | 0.62 (0.55-0.71) | ||||||||||
darunavir/ ritonavir | 600/100 mg b.i.d. | 15 | ↔ | 1.11 (1.01-1.22) | 1.15 (1.05-1.26) | 1.02 (0.90-1.17) | ||||||||||
fosamprenavir/ ritonavir | 700/100 mg b.i.d. | 8 | ↑ | 1.62 (1.47-1.79) | 1.69 (1.53-1.86) | 1.77 (1.39-2.25) | ||||||||||
lopinavir/ ritonavir (soft gel capsule) | 400/100 mg b.i.d. | 14 | ↓ | 0.85 (0.62-1.05) | 0.80 (0.49-1.07) | 0.92 (0.15-1.68) | ||||||||||
| lopinavir/ritonavir (tablet) | 400/100 mg b.i.d. | 16 | ↔ | 0.89 (0.82-0.96) | 0.87 (0.83-0.92) | 0.80 (0.73-0.88) | ||||||||||
lopinavir/ saquinavir/ ritonavir | 400 mg b.i.d./ 800-1000 mg b.i.d./ 100 mg b.i.d. | 11 11 | ↓ LPV ↓ SQV | 0.84 (0.74-0.95) 0.85 (0.61-1.19) | 0.82 (0.70-0.96) 0.87 (0.62-1.21) | 0.76 (0.54-1.08) 0.87 (0.60-1.28) | ||||||||||
saquinavir/ ritonavir | 1000/100 mg b.i.d. | 15 | ↔ | 1.00 (0.70-1.42) | 0.95 (0.64-1.42) | 0.80 (0.46-1.38) | ||||||||||
tipranavir/ ritonavir | 500/200 mg b.i.d. | 19 | ↑ | 1.14 (1.02-1.27) | 1.18 (1.03-1.36) | 1.24 (0.96-1.59) | ||||||||||
| Co-Administration With CCR5 Antagonists | ||||||||||||||||
| maraviroc | 300 mg b.i.d. | 10 | ↓ | 0.40 (0.28-0.57) | 0.47 (0.38-0.58) | 0.61 (0.53-0.71) | ||||||||||
maraviroc/darunavir/ ritonavir *compared to maraviroc 150 mg b.i.d. | 150 mg/600 mg/100 mg b.i.d. | 10 | ↑ | 1.77* (1.20-2.60) | 3.10* (2.57-3.74) | 5.27* (4.51-6.15) | ||||||||||
| Co-Administration With Nucleoside Reverse Transcriptase Inhibitors (NRTIs) | ||||||||||||||||
| didanosine | 400 mg q.d. | 14 | ↔ | 0.91 (0.58-1.42) | 0.99 (0.79-1.25) | N.A. | ||||||||||
| tenofovir disoproxil fumarate | 300 mg q.d. | 19 | ↔ | 1.15 (1.04-1.27) | 1.15 (1.09-1.21) | 1.19 (1.13-1.26) | ||||||||||
| Co-Administration With Integrase Strand Transfer Inhibitors | ||||||||||||||||
| dolutegravir | 50 mg q.d. | 16 | ↓ | 0.48 (0.43 to 0.54) | 0.29 (0.26 to 0.34) | 0.12 (0.09 to 0.16) | ||||||||||
| Co-administered Drug | Dose/Schedule of Co-administered Drug | N | PK | Mean Ratio of Co-administered Drug Pharmacokinetic Parameters 90% CI; No effect = 1.00 | ||||||||||||
|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|
| Cmax | AUC | Cmin | ||||||||||||||
dolutegravir (when co-administered with darunavir/ritonavir) | 50 mg q.d./ 600/100 mg b.i.d. | 9 | ↓ | 0.88 (0.78 to 1.00) | 0.75 (0.69 to 0.81) | 0.63 (0.52 to 0.76) | ||||||||||
dolutegravir (when co-administered with lopinavir/ritonavir) | 50 mg q.d./ 400/100 mg b.i.d. | 8 | ↔ | 1.07 (1.02 to 1.13) | 1.11 (1.02 to 1.20) | 1.28 (1.13 to 1.45) | ||||||||||
| raltegravir | 400 mg b.i.d. | 19 | ↓ | 0.89 (0.68-1.15) | 0.90 (0.68-1.18) | 0.66 (0.34-1.26) | ||||||||||
| Co-Administration With Other Drugs | ||||||||||||||||
atorvastatin 2-hydroxy-atorvastatin | 40 mg q.d. | 16 16 | ↓ ↑ | 1.04 (0.84-1.30) 1.76 (1.60-1.94) | 0.63 (0.58-0.68) 1.27 (1.19-1.36) | N.A. N.A. | ||||||||||
| boceprevir | 800 mg t.i.d. | 20 | ↑ | 1.10 (0.94-1.29) | 1.10 (0.94-1.28) | 0.88 (0.66-1.17) | ||||||||||
clarithromycin 14-hydroxy-clarithromycin | 500 mg b.i.d. | 15 15 | ↓ ↑ | 0.66 (0.57-0.77) 1.33 (1.13-1.56) | 0.61 (0.53-0.69) 1.21 (1.05-1.39) | 0.47 (0.38-0.57) 1.05 (0.90-1.22) | ||||||||||
| digoxin | 0.5 mg single dose | 16 | ↑ | 1.19 (0.96-1.49) | 1.18 (0.90-1.56) | N.A. | ||||||||||
ethinyl estradiol norethindrone | 0.035 mg q.d. 1 mg q.d. | 16 16 | ↑ ↔ | 1.33 (1.21-1.46) 1.05 (0.98-1.12) | 1.22 (1.13-1.31) 0.95 (0.90-0.99) | 1.09 (1.01-1.18) 0.78 (0.68-0.90) | ||||||||||
| fluconazole | 200 mg q.a.m. | 15 | ↔ | 0.92 (0.85-1.00) | 0.94 (0.88-1.01) | 0.91 (0.84-0.98) | ||||||||||
R(-) methadone S(+) methadone | Individual dose regimen ranging from 60 to 130 mg/day | 16 16 | ↔ ↔ | 1.02 (0.96-1.09) 0.89 (0.83-0.97) | 1.06 (0.99-1.13) 0.89 (0.82-0.96) | 1.10 (1.02-1.19) 0.89 (0.81-0.98) | ||||||||||
| paroxetine | 20 mg q.d. | 16 | ↔ | 1.06 (0.95-1.20) | 1.03 (0.90-1.18) | 0.87 (0.75-1.02) | ||||||||||
rifabutin 25-O-desacetylrifabutin | 300 mg q.d. 300 mg q.d. | 12 12 | ↓ ↓ | 0.90 (0.78-1.03) 0.85 (0.72-1.00) | 0.83 (0.75-0.94) 0.83 (0.74-0.92) | 0.76 (0.66-0.87) 0.78 (0.70-0.87) | ||||||||||
| Co-administered Drug | Dose/Schedule of Co-administered Drug | N | PK | Mean Ratio of Co-administered Drug Pharmacokinetic Parameters 90% CI; No effect = 1.00 | ||||||||
|---|---|---|---|---|---|---|---|---|---|---|---|---|
| Cmax | AUC | Cmin | ||||||||||
sildenafil N-desmethyl-sildenafil | 50 mg single dose | 15 15 | ↓ ↓ | 0.55 (0.40-0.75) 0.75 (0.59-0.96) | 0.43 (0.36-0.51) 0.59 (0.52-0.68) | N.A. N.A. | ||||||
| voriconazole | 200 mg b.i.d. | 14 | ↑ | 0.95 (0.75-1.21) | 1.14 (0.88-1.47) | 1.23 (0.87-1.75) | ||||||
CI = Confidence Interval; N = number of subjects with data; N.A. = not available; ↑ = increases; ↓ = decreases; ↔ = no change; q.d. = once daily; b.i.d. = twice daily; t.i.d. = three times daily; q.a.m. = once daily in the morning
- 1. In drug-drug interaction studies, different formulations and/or doses of Intelence were used which led to similar exposures, and, therefore, interactions relevant for one formulation are relevant for the other.
9.5 Drug-Food Interactions
The systemic exposure (AUC) to etravirine was decreased by about 50% when Intelence was administered under fasting conditions, as compared to when Intelence was administered following a meal. Therefore, Intelence should always be taken following a meal. The caloric and fat content of the meal is irrelevant.
Grapefruit or grapefruit juice can inhibit CYP3A enzyme activity and should be avoided with Intelence.
9.6 Drug-Herb Interactions
Concomitant use of Intelence and St. John’s Wort (Hypericum perforatum), or products containing St. John’s Wort, is not recommended. Co-administration of etravirine with St. John’s Wort may cause significant decreases in etravirine plasma concentrations, which may result in loss of therapeutic effect of Intelence (see 9.4 Drug-Drug Interactions, Table 5).
Interactions with other herbal products have not been established.
9.7 Drug-Laboratory Test Interactions
Interactions with laboratory tests have not been established.
10 CLINICAL PHARMACOLOGY
10.1 Mechanism of Action
Etravirine is a non-nucleoside reverse transcriptase inhibitor (NNRTI) of human immunodeficiency virus type 1 (HIV-1). Etravirine binds directly to reverse transcriptase (RT) and blocks the RNA-dependent and DNA-dependent DNA polymerase activities by causing a disruption of the enzyme's catalytic site. Etravirine can bind in at least two conformationally distinct modes. Within a given binding mode, torsional flexibility of etravirine permits access to numerous conformational variants, while the compact design of etravirine permits significant repositioning and reorientation (translation and rotation) within the pocket. Etravirine does not inhibit the human DNA polymerases α, β, and γ.
Decreases in plasma viral load were typically observed as early as 1–2 days after the start of
Intelence administration in monotherapy trials.
Resistance
Development of resistance against etravirine in vitro typically required multiple NNRTI-resistances associated mutations (RAMs) of which the following were observed most frequently: L100I, E138K, E138G, V179I, Y181C and M230I.
In the Phase III trials, DUET-1 and DUET-2, mutations that developed most commonly in subjects with virologic failure to the Intelence-containing regimen were V179F, V179I and Y181C, generally within a background of other NNRTI RAMs (see 15 MICROBIOLOGY Resistance in treatment-experienced subjects).
Cross-Resistance
Limited cross-resistance between etravirine and efavirenz was observed in vitro in 3 of the 65 site-directed HIV-1 mutant strains containing an NNRTI resistance-associated mutation. Cross-resistance to delavirdine, efavirenz and/or nevirapine is expected after virologic failure with an etravirine-containing regimen for the virologic failure isolates. Therefore, the treatment of patients with delavirdine, efavirenz or nevirapine following virologic failure of an etravirine-containing regimen is not recommended (see 15 MICROBIOLOGY, Cross-Resistance In Vitro).
10.3 Pharmacokinetics
The pharmacokinetic properties of etravirine have been evaluated in adult healthy subjects and in adult treatment-experienced HIV-1-infected patients. Exposure to etravirine was slightly lower in HIV-1-infected patients than in healthy subjects.
Table 9: Population Pharmacokinetic Estimates of Etravirine 200 mg b.i.d. in HIV-1-Infected Adult Subjects1 (Integrated Data from Phase III DUET Trials at Week 48)
| Parameter | Etravirine 200 mg b.i.d. N=575 |
|---|---|
| AUC12h (ng•h/mL) | |
| Geometric Mean ± Standard Deviation | 4552 ± 4710 |
| Median (Range) | 4380 (458-59084) |
| C0h (ng/mL) | |
| Geometric Mean ± Standard Deviation | 297±391 |
| Median (Range) | 298 (2-4852) |
- 1. PK values are about 30% higher in healthy volunteers All HIV-infected subjects enrolled in Phase III clinical trials received darunavir/ritonavir 600/100 mg b.i.d. as part of their background regimen. Therefore, the pharmacokinetic parameter estimates account for reductions in the pharmacokinetic parameters of etravirine due to co-administration of Intelence with darunavir/ritonavir.
When Intelence was administered for 8 days to healthy volunteers, the increase in exposure to etravirine was generally dose proportional between total daily doses of 200 and 400 mg, and the total exposure to etravirine was similar irrespective of whether the total daily dose was administered in a once-daily or twice-daily regimen.
Absorption
Maximum etravirine plasma concentrations are generally attained by 4 hours following single or multiple oral doses of 100 mg to 400 mg. Dose-proportional pharmacokinetics were observed for daily doses from 200-400 mg and steady-state plasma concentrations were reached in approximately 7 days.
The population pharmacokinetics derived geometric mean (SD) C0h and AUC12h for etravirine in 574 HIV-1-infected patients receiving Intelence is 4531.53 (±4543.69) ng.h/mL and 296.74 (±377.52) ng/mL, respectively.
An intravenous formulation of etravirine is unavailable: thus, the absolute bioavailability of Intelence is unknown. After oral administration with food, the maximum plasma concentration of etravirine is generally achieved within 4 hours.
In healthy subjects, the absorption of etravirine is not affected by co-administration of oral ranitidine or omeprazole, drugs that are known to increase gastric pH.
Effect of food on oral absorption
The exposure to etravirine is similar when taken following a standard normal caloric meal (561 kcal) or high-fat high caloric meal (1160 kcal). When compared to administration following a standard normal caloric meal, exposure to etravirine was decreased by 51% in fasted conditions. Therefore, to achieve optimal exposure, Intelence should be taken following a meal. The caloric and fat content of the meal is irrelevant. (See 4 DOSAGE AND ADMINISTRATION and 9 DRUG INTERACTIONS; 9.5 Drug-Food Interactions).
Distribution
Etravirine is approximately 99.9% bound to plasma proteins, primarily to albumin (99.6%) and alpha1-acid glycoprotein (94.48-97.66%) in vitro. The distribution of etravirine into compartments other than plasma (e.g. cerebrospinal fluid, genital tract secretions) has not been evaluated in humans.
In rats, the highest concentrations of radiolabelled etravirine and its metabolites were measured in the gastrointestinal tract, liver and adrenal gland and the lowest levels were associated with blood, plasma, brain, lung and bone. There was no evidence of undue retention or accumulation. The elimination of radioactivity was complete in rats within 96 hours of etravirine oral administration.
In pregnant rats, there was distribution of radiolabelled etravirine and its metabolites to the placenta, vagina, uterus, mammary glands and fetus. Total radioactivity levels in placenta and fetus were about twice the levels observed in maternal blood.
Metabolism
In vitro experiments with human liver microsomes (HLMs) indicate that etravirine primarily undergoes oxidative metabolism by CYP3A, CYP2C9 and CYP2C19 enzymes. The major metabolites, formed by methyl hydroxylation of the dimethylbenzonitrile moiety, were at least 90% less active than etravirine against wild-type HIV in cell culture.
Etravirine is not a substrate for P-glycoprotein in in vitro studies. Etravirine is an inhibitor of P-glycoprotein in vitro with a 50% inhibitory concentration (IC50) value of 10,500 ng/mL for the probe paclitaxel. This value is approximately 20-fold higher than the average maximum plasma concentration observed in HIV-1 infected patients and is unlikely to have a clinically relevant impact. The extent of first-pass metabolism of etravirine has not been evaluated due to the absence of a suitable intravenous formulation. Etravirine has no pharmacologically active metabolites in the presence of NNRTI-resistant strains of HIV. No dose-dependent changes in metabolism have been observed for etravirine over the daily dose range of 200-400 mg.
Elimination
The terminal elimination half-life of etravirine is approximately 30-40 hours. After administration of a radiolabelled 14C-etravirine dose, 93.7% and 1.2% of the administered radioactivity could be retrieved in feces and urine, respectively. Unchanged etravirine accounted for 81.2%-86.4% of the administered dose in feces while no unchanged etravirine could be detected in urine.
After administration of a radiolabelled 14C-etravirine dose in human subjects, 93.7% and 1.2% of the administered dose of 14C-etravirine could be retrieved in feces and urine, respectively. Unchanged etravirine accounted for 81.2% to 86.4% of the administered dose in feces. Unchanged etravirine was not detected in urine.
Effects on Electrocardiogram
In a randomized, double-blind, active- and placebo-controlled crossover study, 41 healthy male and female volunteers were administered Intelence 200 mg b.i.d., Intelence 400 mg q.d., placebo and moxifloxacin 400 mg. After 8 days of dosing, etravirine did not prolong the QT interval. The placebo-adjusted mean maximum increases in QTcF from baseline after 200 mg b.i.d. and 400 mg q.d. of etravirine were 0.1 msec and -0.2 msec, respectively, and 10.1 msec for moxifloxacin 400 mg q.d. No subject in any group had an increase in QTcF of >60 msec. No subject experienced an interval exceeding the potentially clinically relevant threshold of 500 msec.
Special Populations and Conditions
- Pediatrics
The pharmacokinetics of etravirine in 101 treatment-experienced HIV-1-infected pediatric subjects, 6 years to <18 years of age and weighing at least 16 kg (35.2 lbs), showed that the administered weight-based dosages resulted in etravirine exposure comparable to that in adults receiving Intelence 200 mg twice daily (see 4 DOSAGE AND ADMINISTRATION and 10 CLINICAL PHARMACOLOGY) when administered at a dose corresponding to 5.2 mg/kg twice daily. The population pharmacokinetic estimates for etravirine AUC12h and C0h are summarized in the table below.
Table 10: Population Pharmacokinetic Estimates for Etravirine (all doses combined) in Treatment-Experienced HIV-1-Infected Pediatric Subjects 6 years to <18 years of age (PIANO 24 and 48 weeks analysis)
| Outcome at Week 24 | Outcome at Week 48 | ||||||||||
|---|---|---|---|---|---|---|---|---|---|---|---|
| Parameter | N = 101 | N = 101 | |||||||||
| AUC12h (ng•h/mL) | |||||||||||
| Geometric Mean ± Standard Deviation | 3742 ± 4314 | 3729 ± 4305 | |||||||||
| Median (Range) | 4499 (62 - 28865) | 4560 (62 – 28865) | |||||||||
| C0h (ng/mL) | |||||||||||
| Geometric Mean ± Standard Deviation | 205 ± 342 | 205 ± 342 | |||||||||
| Median (Range) | 287 (2 - 2276) | 287 (2 - 2276) | |||||||||
The pharmacokinetics of etravirine in pediatric patients (<6 years of age) are under investigation. There are insufficient data at this time to recommend a dose in pediatric patients <6 years of age.
- Geriatrics
Population pharmacokinetic analysis in HIV-infected subjects showed that etravirine pharmacokinetics are not considerably different in the age range (18 to 77 years) evaluated (see 7.1.4 Geriatrics).
- Sex
A limited number of women were included in studies. The pharmacokinetics of etravirine in HIV-1-infected patients appears to be similar between men and women.
- Pregnancy and Breast-feeding
The total etravirine exposure after intake of Intelence 200 mg b.i.d. as part of an antiretroviral regimen was generally higher during pregnancy compared with postpartum (see Table 11). The differences were less pronounced for unbound etravirine exposure.
In women receiving Intelence 200 mg b.i.d., higher mean values for Cmax, AUC12h and Cmin were observed during pregnancy compared to postpartum. During the 2nd and 3rd trimester of pregnancy mean values of these parameters were comparable.
Table 11: Pharmacokinetic results of total etravirine after administration of etravirine 200 mg b.i.d. as part of an antiretroviral regimen, during the 2nd trimester of pregnancy, the 3rd trimester of pregnancy, and postpartum.
| Pharmacokinetics of etravirine (mean ±SD, median) | Intelence 200 mg b.i.d. postpartum | Intelence 200 mg b.i.d. 2nd trimester | Intelence 200 mg b.i.d. 3rd trimester |
| N | 10 | 13 | 101 |
| Cmin, ng/mL | 269 ± 182 284 | 383 ± 210 346 | 349 ± 103 371 |
| Cmax, ng/mL | 569 ± 261 528 | 774 ± 300 828 | 785 ± 238 694 |
| AUC12h, ng•h/mL | 5004 ± 2521 5246 | 6617 ± 2766 6836 | 6846 ± 1482 6028 |
- 1. n=9 for AUC12h
Each subject served as her own control, and with an intra-individual comparison, the total etravirine Cmin, Cmax and AUC12h values were 1.2-, 1.4- and 1.4-fold higher, respectively, during the 2nd trimester of pregnancy as compared to postpartum, and 1.1-, 1.4- and 1.2-fold higher, respectively, based during the 3rd trimester of pregnancy as compared to postpartum.
- Ethnic Origin
Population pharmacokinetic analysis of etravirine in HIV-infected patients indicated that race had no apparent effect on the exposure to etravirine.
- Hepatic Insufficiency
Hepatic Impairment
Etravirine is primarily metabolized and eliminated by the liver. In a study comparing 8 patients with mild hepatic impairment to 8 matched controls and 8 patients with moderate hepatic impairment to 8 matched controls, the multiple dose pharmacokinetic disposition of etravirine was not altered in patients with mild to moderate hepatic impairment. No dosing adjustment is required in patients with mild or moderate hepatic impairment. Intelence has not been studied in patients with severe hepatic impairment (see 7 WARNINGS AND PRECAUTIONS and 4 DOSAGE AND ADMINISTRATION).
Hepatitis B or Hepatitis C Virus Co-infection
Population pharmacokinetic analysis of the DUET-1 and DUET-2 trials showed reduced clearance for Intelence in HIV-1-infected subjects with hepatitis B and/or C virus co-infection. Based upon the safety profile, no dose adjustment is necessary in patients co-infected with hepatitis B and/or C virus.
- Renal Insufficiency
The pharmacokinetics of etravirine have not been studied in patients with renal insufficiency. Results from a mass balance study with radioactive 14C-etravirine showed that <1.2% of the administered dose of etravirine is excreted in the urine. No unchanged drug was detected in urine so the impact of renal impairment on etravirine elimination is expected to be minimal. As etravirine is highly bound to plasma proteins, it is unlikely that it will be significantly removed by hemodialysis or peritoneal dialysis (see 7 WARNINGS AND PRECAUTIONS, Renal and 4 DOSAGE AND ADMINISTRATION, Recommended Dose and Dosage Adjustment, Renal Impairment).
11 STORAGE, STABILITY AND DISPOSAL
Store Intelence tablets between 15–30°C. Store in the original bottle. Keep the bottle tightly closed in order to protect from moisture. Do not remove the desiccant pouches.
Keep out of the reach and sight of children.
12 SPECIAL HANDLING INSTRUCTIONS
Not Applicable.
PART II: SCIENTIFIC INFORMATION
13 PHARMACEUTICAL INFORMATION
Drug Substance
Proper name:
etravirine
Chemical name:
4-[[6-amino-5-bromo-2-[(4-cyanophenyl)-amino]-4-pyrimidinyl]oxy]-3,5-dimethylbenzonitrile
Molecular formula and molecular mass:
Molecular formula: C20H15BrN6O
Molecular mass: 435.28
Structural formula:
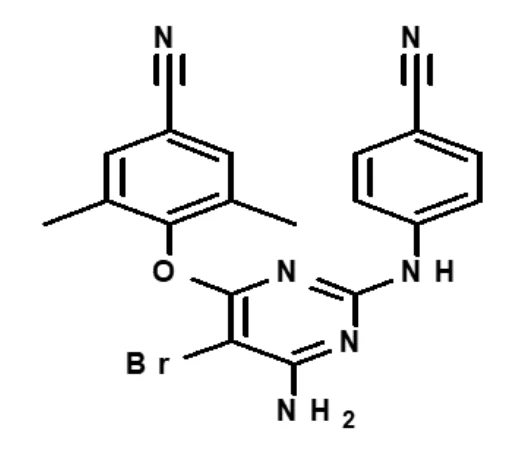
Physicochemical properties:
Etravirine is a white to slightly yellowish-brown powder with a solubility in water of <0.001 g/100 mL at 20oC.
14 CLINICAL TRIALS
14.1 Clinical Trials by Indication
Treatment-Experienced Adult Patients
Trials TMC125-C206(DUET) and TMC125-216(DUET-2)
The evidence of efficacy of INTELENCE® (etravirine) is based on the analyses of 48-week data from 2 randomized, double-blinded, placebo-controlled, Phase III trials DUET-1 and DUET-2. These trials were identical in design, and similar efficacy for Intelence was seen in each trial. The results below are pooled data from the two trials.
Treatment-experienced HIV-1-infected adult subjects who had plasma HIV-1 RNA >5000 copies/mL and had 1 or more NNRTI resistance-associated mutations at screening or from prior genotypic analysis (i.e., archived resistance) were enrolled. These subjects also had 3 or more of the following primary PI mutations: D30N, V32I, L33F, M46I/L, I47A/V, G48V, I50L/V, V82A/F/L/S/T, I84V, N88S, or L90M at screening, and were on a stable antiretroviral regimen for at least 8 weeks. Randomization was stratified by the intended use of enfuvirtide in the BR, previous use of darunavir/ritonavir, and screening viral load. This analysis included 612 subjects in DUET-1 and 591 subjects in DUET-2 who had completed 48 weeks of treatment or discontinued earlier.
At 48 weeks, the virologic response rate was evaluated in subjects receiving Intelence (200 mg b.i.d.) in addition to a BR versus subjects receiving placebo in addition to a BR. The BR consisted of darunavir/ritonavir 600/100 mg b.i.d. and at least 2 other investigator-selected antiretroviral drugs (N[t]RTIs with or without enfuvirtide).
45.6% of subjects in the Intelence arm and 46.9% of subjects in the placebo arm used enfuvirtide in the underlying antiretroviral therapy. 25.5% of subjects in the Intelence arm used enfuvirtide for the first time (de novo), compared with 26.5% of subjects in the placebo arm. 20.0% of subjects in the Intelence arm re-used enfuvirtide, compared with 20.4% of subjects in the placebo arm. Virologic response was defined as achieving a confirmed undetectable viral load (<50 HIV-1 RNA copies/mL).
In the pooled analysis for DUET-1 and DUET-2, demographics and baseline characteristics were balanced between the Intelence arm and the placebo arm. Table 12 describes the demographic and baseline disease characteristics of the subjects in the Intelence arm and subjects in the placebo arm.
Table 12: Demographic and Baseline Disease Characteristics of Adult Subjects in the DUET-1 and DUET-2 Trials (Pooled Analysis)
| Pooled DUET Trials | DUET–1 | DUET–2 | ||||||||||||||||
|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|
Placebo N = 604 | Intelence N = 599 | Placebo N = 308 | Intelence N = 304 | Placebo N = 296 | Intelence N = 295 | |||||||||||||
| Demographic Characteristics | ||||||||||||||||||
| Median Age, years (range) | 45 (18-72) | 46 (18-77) | 45 (18-72) | 45 (18-67) | 45 (20-69) | 46 (31-77) | ||||||||||||
| Sex | ||||||||||||||||||
| Male | 89% | 90% | 86% | 87% | 92% | 94% | ||||||||||||
| Female | 11% | 10% | 14% | 13% | 8% | 6% | ||||||||||||
| Race | ||||||||||||||||||
| White | 70% | 70% | 65% | 65% | 76% | 77% | ||||||||||||
| 13% | 13% | 12% | 13% | 14% | 13% | |||||||||||||
| Hispanic | 12% | 11% | 14% | 14% | 10% | 8% | ||||||||||||
| Asian | 1% | 1% | 1% | 1% | 0% | 2% | ||||||||||||
| Other | 4% | 4% | 8% | 7% | 0% | 1% | ||||||||||||
| Baseline Disease Characteristics | ||||||||||||||||||
| Median Baseline Plasma HIV-1 RNA (range), log10copies/mL | 4.8 (2.2-6.5) | 4.8 (2.7-6.8) | 4.9 (2.4-6.5) | 4.8 (2.7-6.2) | 4.8 (2.2-6.3) | 4.8 (3.0-6.8) | ||||||||||||
| Pooled DUET Trials | DUET–1 | DUET–2 | |||||||||||||||||||
|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|
Placebo N = 604 | Intelence N = 599 | Placebo N = 308 | Intelence N = 304 | Placebo N = 296 | Intelence N = 295 | ||||||||||||||||
| Percentage of Subjects with Baseline Viral Load: | |||||||||||||||||||||
| <30,000 copies/mL | 28.8% | 27.5% | 27.3% | 26.6% | 30.4% | 28.5% | |||||||||||||||
| ≥30,000 and <100,000 copies/mL | 35.3% | 34.4% | 31.8% | 34.2% | 38.9% | 34.6% | |||||||||||||||
| ≥100,000 copies/mL | 35.9% | 38.1% | 40.9% | 39.1% | 30.7% | 36.9% | |||||||||||||||
| Median Baseline CD4+ Cell Count (range), 106 cells/L | 109 (0–912) | 99 (1–789) | 109 (1–694) | 99 (1–789) | 108 (0–912) | 100 (1–708) | |||||||||||||||
| Percentage of Subjects with Baseline CD4+ Cell Count: | |||||||||||||||||||||
| <50 cells/mm3 | 34.7% | 35.6% | 36.5% | 34.7% | 32.8% | 36.6% | |||||||||||||||
| ≥50 and <200 cells/mm3 | 34.5% | 34.8% | 33.9% | 34.0% | 35.1% | 35.6% | |||||||||||||||
| ≥200 cells/mm3 | 30.8% | 29.6% | 29.7% | 31.4% | 32.1% | 27.8% | |||||||||||||||
| Median (range) Number of PI Mutations1 | 4 (8) | 4 (0-7) | 4 (8) | 4 (0-7) | 4 (0-8) | 4 (0-7) | |||||||||||||||
| Percentage of Subjects with Previous Use of NNRTIs: | |||||||||||||||||||||
| 0 | 7.9% | 8.2% | 6.5% | 6.9% | 9.5% | 9.5% | |||||||||||||||
| 1 | 46.7% | 46.9% | 48.4% | 50.0% | 44.9% | 43.7% | |||||||||||||||
| >1 | 45.4% | 44.9% | 45.1% | 43.1% | 45.6% | 46.8% | |||||||||||||||
| Percentage of Subjects with Previous Use of the Following NNRTIs: | |||||||||||||||||||||
| Efavirenz | 72.5% | 70.3% | 73.7% | 72.4% | 71.3% | 68.1% | |||||||||||||||
| Nevirapine | 58.6% | 57.1% | 58.4% | 56.9% | 58.8% | 57.3% | |||||||||||||||
| Delavirdine | 12.6% | 13.7% | 13.0% | 8.2% | 12.5% | 19.3% | |||||||||||||||
| Median (range) Number of NNRTI RAMs2: | 2 (0-7) | 2 (0-7) | 2 (0-7) | 2 (0-7) | 2 (0-6) | 2 (0-6) | |||||||||||||||
| Median Fold Change of the Virus for the Following NNRTIs: | |||||||||||||||||||||
| Delavirdine | 26.1 | 27.3 | 32.3 | 27.1 | 23.0 | 27.5 | |||||||||||||||
| Efavirenz | 45.4 | 63.9 | 72.8 | 99.8 | 25.0 | 39.9 | |||||||||||||||
| Pooled DUET Trials | DUET–1 | DUET–2 | |||||||||||||||||||
|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|
Placebo N = 604 | Intelence N = 599 | Placebo N = 308 | Intelence N = 304 | Placebo N = 296 | Intelence N = 295 | ||||||||||||||||
| Etravirine | 1.5 | 1.6 | 1.4 | 1.6 | 1.7 | 1.6 | |||||||||||||||
| Nevirapine | 74.0 | 74.3 | 73.7 | 74.3 | 74.3 | 77.3 | |||||||||||||||
| Percentage of Subjects with Previous Use of Enfuvirtide | 42.2% | 39.6% | 34.4% | 30.6% | 50.3% | 48.8% | |||||||||||||||
Percentage of Subjects with a Phenotypic Sensitivity Score (PSS) for the background therapy3 of: 0 1 2 ≥3 | 16.2% 38.7% 27.8% 17.3% | 17.0% 36.5% 26.9% 19.7% | 16.4% 35.1% 31.8% 16.8% | 17.3% 38.2% 23.6% 20.9% | 16.1% 42.5% 23.6% 17.7% | 16.7% 34.7% 30.3% 18.4% | |||||||||||||||
RAMs = Resistance-Associated Mutations
FC = fold change in EC50
- 1. IAS-USA primary PI mutations [August/September 2007], D30N, V32I, L33F, M46I/L, I47A/V, G48V, I50L/V, I54L/M, L76V, V82A/F/L/S/T, I84V, N88S, L90M
- 2. Tibotec NNRTI RAMs [June 2008]: A98G, V90I, L100I, K101E/H/P/Q, K103H/N/S/T, V106A/M/I, V108I, E138A/G/K/Q, V179D/E/F/G/I/T, Y181C/I/V, Y188C/H/L, V189I, G190A/C/E/Q/S, H221Y, P255H, F227C/L, M230I/L, P236L, K238N/T, Y318F
- 3. The PSS was calculated for the background therapy (as determined on Day 7). Percentages are based on the number of subjects with available phenotype data. For fusion inhibitors (enfuvirtide), subjects were considered resistant if the drug was used in previous therapy up to baseline. Intelence is not included in this calculation.
Study results
Table 13 below presents the efficacy results at 48 weeks for adult patients in the Intelence arm and patients in the placebo arm from the pooled DUET-1 and DUET-2 trials.
At Week 24 a statistically significant interaction (p=0.0064, Breslow-Day test) between treatment and enfuvirtide use was seen. The interaction effect was still significant at Week 48 (p=0.1279). Therefore, the primary analysis at Week 48 was performed for each enfuvirtide stratum: “Re-Used/Not Used Enfuvirtide” [patients re-using or not using enfuvirtide] and “De novo Enfuvirtide use”.
Table 13: Outcomes of Treatment at Week 48 of the DUET-12 and DUET-22 Trials (pooled analysis)
| Outcomes | De Novo Enfuvirtide use | Re-Used/Not Used Enfuvirtide | |||||||
|---|---|---|---|---|---|---|---|---|---|
Placebo + BR N=159 | Intelence + BR N=153 | Placebo + BR N=445 | Intelence + BR N=446 | ||||||
| Virologic Responders | |||||||||
| Viral Load <50 HIV-1 RNA copies/mL1 | 93 (58.5%) | 109 (71.2%)1 | 147 (33.0%) | 254 (57.0%)1 | |||||
| Outcomes | De Novo Enfuvirtide use | Re-Used/Not Used Enfuvirtide | ||||||||||||
|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|
Placebo + BR N=159 | Intelence + BR N=153 | Placebo + BR N=445 | Intelence + BR N=446 | |||||||||||
| Viral Load <400 HIV-1 RNA copies/mL1 | 110 (69.2%) | 125 (81.7%) | 176 (39.6%) | 303 (67.9%) | ||||||||||
| Mean change from baseline in log10 HIV-1 RNA | -2.22 (0.11) | -2.60 (0.10) | -1.23 (0.07) | -2.13 (0.07) * | ||||||||||
| Mean change from baseline in CD4 cell count | 111.4 (9.3) | 134.5 (10.0) | 59.2 (5.0) | 85.7 (5.0) | ||||||||||
| Virologic Failures | 52 (32.7) | 30 (19.6) | 248 (55.7) | 147 (33.0) | ||||||||||
| Viral Load ≥50 HIV-1 RNA copies/mL | 17 (10.7%) | 16 (10.5%) | 30 (6.7%) | 50 (11.2%) | ||||||||||
| Death | 4 (2.5%) | 4 (2.6%) | 16 (3.6%) | 7 (1.6%) | ||||||||||
| Discontinuation due to Adverse Event | 3 (1.9%) | 7 (4.6%) | 11 (2.5%) | 24 (5.4%) | ||||||||||
| Discontinuation due to Other Reasons | 7 (4.4%) | 3 (2.0%) | 23 (5.2%) | 14 (3.1%) | ||||||||||
1 Imputations according to the TLOVR algorithm
NS: p>0.05, *: p<0.0001; p-values Intelence vs. placebo
BR – background regimen consisting of DRV/rtv + minimum of 2 commercially available ARVs consisting of NRTI(s) with or without ENFUVIRTIDE.
- 1. p-value vs. placebo from CMH test controlling for previous DRV use and baseline viral load.
- 2. DUET 1 & 2 are ongoing 96-week clinical trials.
At Week 48, AIDS-defining illness or death occurred in 5.8% of Intelence-treated subjects and 9.8% of placebo-treated subjects.
The proportion of virologic responders (viral load <50 HIV-1 RNA copies/mL) by the Phenotypic Sensitivity Score (PSS) of the background therapy, including enfuvirtide, is shown in Table 14.
Table 14: Virologic Response (Viral Load <50 HIV-1 RNA copies/mL) at Week 48 by Phenotypic Sensitivity Score (PSS) in the Non-Viral Failure Excluded Population of TMC125-C206 and TMC125-C216 Trials (Pooled Analysis)
Intelence + BR N=539 | Placebo + BR N=536 | |
|---|---|---|
| PSS1 | ||
| 0 | 46% (40/87) | 6% (5/83) |
| 1 | 63% (125/200) | 32% (64/201) |
| 2 | 79% (114/145) | 62% (97/156) |
| ≥ 3 | 78% (83/107) | 75% (72/96) |
- 1. In the calculation of the PSS, darunavir was counted as a sensitive antiretroviral if the FC ≤ 10; enfuvirtide was counted as a sensitive antiretroviral if it had not been used previously. Intelence was not included in this calculation.
Trial TMC125-C227
Trial TMC125-C227 was a randomized, exploratory, active-controlled, open-label, Phase IIb trial. Eligible adult subjects were treatment-experienced, PI-naïve HIV-1-infected patients with genotypic evidence of NNRTI resistance at screening or from prior genotypic analysis. The virologic response was evaluated in 116 subjects who were randomized to Intelence (n=59) or an investigator-selected PI (n=57), each given with 2 investigator-selected N(t)RTIs. Compared to the control PI-treated subjects, Intelence-treated subjects had lower antiviral responses associated with reduced susceptibility to the N(t)RTIs and to Intelence.
Treatment-Experienced Pediatric Patients
(6 years to <18 years of age)
PIANO (TMC-125-C213) is a single-arm, Phase II trial evaluating the pharmacokinetics, safety, tolerability, and efficacy of Intelence in 101 antiretroviral treatment-experienced HIV-1 infected pediatric subjects 6 years to < 18 years of age and weighing at least 16 kg (35.2 lbs). The study enrolled subjects on a stable but virologically failing antiretroviral treatment regimen, with a confirmed HIV-1 RNA plasma viral load ≥500 copies/mL. Sensitivity of the virus to Intelence at screening was required.
The median baseline plasma HIV-1 RNA was 3.9 log10 copies/mL, and the median baseline CD4 cell count was 385 × 106 cells/L.
The virologic response rate was evaluated in pediatric subjects receiving Intelence in combination with other antiretroviral agents (see 4 DOSAGE AND ADMINISTRATION for dosage recommendations per body weight). Virologic response was defined as the percentage of subjects with plasma viral load <50 HIV-1 copies/mL at week 24 or Week 48 calculated according to the TLOVR imputation algorithm.
At Week 24, 51.5% of all pediatric subjects had an undetectable viral load <50 HIV-1 RNA copies/mL. The proportion of pediatric subjects with <400 HIV-1 RNA copies/mL was 65.3%. The mean change in plasma HIV-1 RNA from baseline to Week 24 was -1.51 log10 copies/mL, and the mean CD4 cell count increase from baseline was 112 × 106 cells/L.
At Week 48, 53.5% of all pediatric patients had a confirmed undetectable viral load <50 HIV-1 RNA copies/mL. The proportion of pediatric patients with <400 HIV-1 RNA copies/mL was 63.4%. The mean change in plasma HIV-1 RNA from baseline to Week 48 was -1.53 log10 copies/mL, and the mean CD4 cell count increase from baseline was 156 × 106 cells/L.
14.2 Comparative Bioavailability Studies
Pivotal Comparative Bioavailability Study
In a Phase I, open-label, randomized, 4-period crossover bioavailability trial, the relative oral bioavailability of etravirine administered as either two Intelence (etravirine) 100 mg non-coated tablets (Treatment A; F060), two etravirine 100 mg coated tablets (Treatment B; F069), one etravirine 200 mg non-coated tablet (Treatment C; F068), or one etravirine 200 mg coated tablet (Treatment D; F070) under fed conditions (21 g fat; 533 kcal) was assessed in 24 healthy male and female adult subjects
A summary of the results based on the comparison between the current marketed Intelence (etravirine)100 mg non-coated tablets (F060; Treatment A [n=24] and the proposed for marketed etravirine 200 mg non-coated tablets (F068); Treatment C [n=23]) is presented in Table 15.
Table 15: Summary Table of the Comparative Bioavailability Data Under Fed Conditions
Etravirine (TMC125) 1 x 200 mg tablet (F068) and 2 x 100 mg tablets(F060) From measured data Geometric Mean Arithmetic Mean (CV%) | ||||
|---|---|---|---|---|
| Parameter1 | Test2 | Reference3 | % Ratio of Geometric Means | 90% Confidence Interval |
| AUC0-72 (ng.h/mL) | 3741 4247 (50.81) | 3697 4037 (42.95) | 98.26 | 90.61 – 106.6 |
Cmax (ng/mL) | 389 425(46.62) | 369 392 (37.59) | 103.3 | 94.42 – 113.0 |
Tmax4 (h) | 4.0 (2.0 – 6.0) | 5.0 (2.0- 6.0) | ||
- 1. Due to the design of the study AUCI and T1/2 parameters could not be accurately estimated.
- 2. Etravirine 200 mg non-coated tablets (F068) (Janssen Inc.)
- 3. Intelence (etravirine) 100 mg non-coated tablets (F060) (Janssen Inc.)
- 4. Expressed as the median (range) only.
15 MICROBIOLOGY
Antiviral Activity In Vitro
Etravirine exhibits activity against laboratory strains and clinical isolates of wild-type HIV-1 in acutely infected T-cell lines, human peripheral blood mononuclear cells, and human monocytes/macrophages with median EC50 values ranging from 0.9 to 5.5 nM (i.e., 0.4 to 2.4 ng/mL).
Etravirine demonstrated antiviral activity in cell culture against a broad panel of HIV-1 group M isolates (subtype A, B, C, D, E, F, G) with EC50 values ranging from 0.29 to 1.65 nM and EC50 values ranging from 11.5 to 21.7 nM against group O primary isolates. These EC50 values are well below the 50% cellular toxicity concentration range of 15 to >100 µM.
The EC50 value of etravirine for HIV-1 increases by a median factor of 5.8 in the presence of human serum.
No antagonism is observed between etravirine and any of the studied antiretrovirals. Etravirine shows additive antiviral activity in combination with the PIs amprenavir, atazanavir, darunavir, indinavir, lopinavir, nelfinavir, ritonavir, tipranavir, and saquinavir; the N(t)RTIs zalcitabine, didanosine, stavudine, abacavir, and tenofovir; the NNRTIs efavirenz, delavirdine, and nevirapine; the fusion inhibitor enfuvirtide; the integrase inhibitor raltegravir and the CCR5 antagonist maraviroc. Etravirine shows additive to synergistic antiviral activity in combination with the NRTIs emtricitabine, lamivudine, and zidovudine.
Resistance In Vitro
Etravirine showed antiviral activity against 55 of 65 HIV-1 strains with single amino acid substitutions at RT positions associated with NNRTI resistance, including the K103N. The amino acid substitutions which led to the highest resistance to etravirine in cell culture are Y181I (13-fold change in EC50 value) and Y181V (17-fold change in EC50 value). The antiviral activity of etravirine in cell culture against 24 HIV-1 strains with multiple amino acid substitutions associated with resistance to N(t)RTIs and/or PIs is comparable to that observed against wild type HIV-1.
In vitro selection of etravirine-resistant strains originating from wild type HIV-1 of different origins and subtypes as well as NNRTI-resistant HIV-1 was performed at high and low virus inoculum. At high virus inoculum, emergence of resistant strains from wild type HIV-1 was delayed or prevented at concentrations of 40 nM or 200 nM. Regardless of the experimental design and the original HIV-1 strain, development of resistance against etravirine typically required multiple mutations in the RT of which the following were observed most frequently: L100I, E138K, E138G, V179I, Y181C, and M230I.
Resistance in treatment-experienced subjects
In the Phase III trials DUET-1 and DUET-2, mutations that developed most commonly in subjects with virologic failure to the Intelence-containing regimen were V179F, V179I and Y181C which usually emerged in a background of multiple other NNRTI resistance-associated mutations (RAMs). In all the trials conducted with Intelence in HIV-1 infected subjects, the following mutations emerged most commonly: L100I, E138G, V179F, V179I, Y181C and H221Y.
Cross-Resistance In Vitro
The single amino acid substitutions associated with an etravirine reduction in susceptibility >3-fold were K101A, K101P, K101Q, E138G, E138Q, Y181C, Y181I, Y181T, Y181V, and M230L, and of these, the greatest reductions were Y181I (13-fold change in EC50 values) and Y181V (17-fold change in EC50 value). Mutant strains containing a single NNRTI resistance associated substitution (K101P, K101Q, E138Q, or M230L) had cross-resistance between etravirine and efavirenz. The majority (39 of 61; 64%) of the NNRTI mutant viruses with 2 or 3 amino acid substitutions associated with NNRTI resistance had decreased susceptibility to etravirine (fold-change >3). The highest levels of resistance to etravirine were observed for HIV-1 harbouring a combination of substitutions V179F + Y181C (181 fold-change), V179 + Y181I (123 fold-change), or V179F + Y181C + F227C (888 fold-change). Etravirine retains an EC50 value <10 nM against 83% of 6171 clinical isolates resistant to delavirdine, efavirenz and/or nevirapine. The treatment of patients with delavirdine, efavirenz or nevirapine following virologic failure of an etravirine-containing regimen is not recommended.
Baseline Genotype/Phenotype and Virologic Outcome Analyses
In DUET-1 and DUET-2, the presence at baseline of three or more of the following mutations: V90I, A98G, L100I, K101E, K101P, V106I, V179D, V179F, Y181C, Y181I, Y181V, G190A, and G190S (Intelence-RAMs) was associated with a decreased virologic response to Intelence (see Table 16). These individual mutations mainly occurred in the presence of other NNRTI RAMs. V179F was never present without Y181C.
K103N, which was the most prevalent NNRTI mutation in DUET-1 and DUET-2 at baseline, was not identified as a mutation associated with resistance to Intelence. The presence of this mutation did not affect the response in the Intelence arm.
Table 16: Proportion of Subjects with <50 HIV-1 RNA copies/mL at Week 48 by Baseline Number of TMC125 Resistance Associated Mutations (RAMs) in the non-Viral Failure excluded Population of the Pooled DUET Studies
| Number of TMC125 RAMs1 | Etravirine Arms N=540 | Placebo Arms N=541 | |||||||||||
|---|---|---|---|---|---|---|---|---|---|---|---|---|---|
| Re-Used/Not Used Enfuvirtide | De Novo Enfuvirtide | Re-Used/Not Used Enfuvirtide | De Novo Enfuvirtide | ||||||||||
| All ranges | 63.3% (254/401) | 78.4% (109/139) | 37.1% (147/396) | 64.1% (93/145) | |||||||||
| 0 | 74.1% (117/158) | 91.3% (42/46) | 42.7% (61/143 | 73.6% (39/53) | |||||||||
| 1 | 61.3% (73/119) | 80.4% (41/51) | 38.6% (59/153) | 64.7% (33/51) | |||||||||
| 2 | 64.1% (41/64) | 66.7% (18/27) | 26.2% (16/61) | 52.6% (10/19) | |||||||||
| ≥3 | 38.3% (23/60) | 53.3% (8/15) | 28.2% (11/39) | 50.0% (11/22) | |||||||||
- 1. TMC125 RAMs = V90I, A98G, L100I, K101E/P, V106I, V179D/F, Y181C/I/V, G190A/S
Conclusions regarding the relevance of particular mutations or mutational patterns are subject to change pending additional data.
Response rates assessed by baseline etravirine phenotype are shown in Table 17. These baseline phenotype groups are based on the select subject populations in DUET-1 and DUET-2 and are not meant to represent definitive clinical susceptibility breakpoints for Intelence. The data are provided to give clinicians information on the likelihood of virologic success based on pre-treatment susceptibility to etravirine in treatment-experienced patients.
Table 17: Proportion of Subjects with <50 HIV-1 RNA copies/mL at Week 48 by Baseline Phenotype and Enfuvirtide Use in the Pooled DUET studies1
Etravirine Fold Change | Etravirine Arms N=539 | Placebo Arms N=534 | ||||||||
|---|---|---|---|---|---|---|---|---|---|---|
| Re-Used/Not Used Enfuvirtide | De Novo Enfuvirtide | Re-Used/Not Used Enfuvirtide | De Novo Enfuvirtide | |||||||
| All ranges | 63% (253/400) | 78% (109/139) | 37% (145/391) | 64% (92/143) | ||||||
| 0 – ≤3 | 70% (188/267) | 85% (78/88) | 43% (112/262) | 64% (61/95) | ||||||
| >3 – ≤13 | 53% (39/74) | 68% (25/37) | 29% (22/77) | 69% (18/26) | ||||||
| >13 | 44% (26/59) | 64% (9/14) | 21% (11/52) | 59% (13/22) | ||||||
- 1. non-VF Excluded Population
In deciding on a new regimen for patients who have failed an antiretroviral regimen, careful consideration should be given to the treatment history and to resistance testing results where available.
16 NON-CLINICAL TOXICOLOGY
General Toxicology:
Acute Toxicity
In mice and rats, there were no relevant effects following oral or subcutaneous administration of etravirine at doses up to 1000 and 320 mg/kg, respectively. Similarly, in dogs there was no effect of etravirine treatment following oral administration at doses up to 160 mg/kg.
Chronic Toxicity
Chronic repeat dose toxicity studies were conducted in mice (3 month duration), rats (6 month duration) and dogs (12 month duration). In mice the key target organs identified were the liver and the coagulation system. Haemorrhagic cardiomyopathy was only observed in male mice and was considered to be secondary to severe coagulopathy mediated via the vitamin K pathway. This is considered not relevant to humans. In the rat, the key target organs identified were the liver, the thyroid, and the coagulation system. Exposure in mice was equivalent to human exposure while in rats it was below the clinical exposure at the recommended dose (200 mg b.i.d.).
In the dog, changes in the liver and gall bladder were seen at exposures approximately 8-fold higher than human exposure observed at the recommended dose (200 mg b.i.d.).
Carcinogenicity: Etravirine was evaluated for carcinogenic potential by oral gavage administration to mice and rats up to 104 weeks. A statistically significant increase in the incidences of hepatocellular adenomas and carcinomas was observed in treated female mice. Administration of etravirine did not cause a statistically significant increase in the incidence of tumors in female or male rats. The relevance of the findings in mice to humans is not known. At the highest tested doses, the systemic exposures (based on AUC) to etravirine were lower than those in humans at the clinical therapeutic dose (200 mg b.i.d.) with animal versus human AUC ratios being 0.6 (mice) and between 0.2 and 0.7 (rats).
Genotoxicity: In a range of mutagenicity studies, etravirine tested negative in the in vitro Ames reverse mutation assay, in vitro chromosomal aberration assay in human lymphocytes, and in vitro clastogenicity mouse lymphoma assay, in the absence and presence of a metabolic activation system. Etravirine did not induce chromosomal damage in the in vivo micronucleus test in mice.
Reproductive and Developmental Toxicology: In a study conducted in rats, there were no effects on mating or fertility with etravirine treatment up to 500 mg/kg/day and exposure levels equivalent to those in humans at the clinically recommended dose.
There was no teratogenicity with etravirine in rats (1000 mg/kg) and rabbits (375 mg/kg) at exposures equivalent to those observed in humans at the recommended clinical dose. In a pre- and postnatal development assessment in rats, etravirine had no effect on offspring development during lactation or post-weaning when the mother was dosed up to 500 mg/kg and at exposures equivalent to those observed at the recommended clinical dose.
Local Tolerance: Etravirine was classified as “nonsensitizing” based on an in vivo guinea pig skin sensitization study and was also found to be unlikely to cause skin sensitization in a mouse local lymph node assay. Etravirine was also classified as “nonirritant” based on an in vivo rabbit skin irritation study. In an in vitro eye irritation assay, etravirine was considered as a “mild” eye irritant. No effects were observed in an in vitro phototoxicity study.
Immunotoxicity: Immunotoxicity has been evaluated in rats. Etravirine was administered at a dose of 600 mg/kg/day for 4 weeks and effects on lymphoid organs (lymph nodes, spleen and thymus) were evaluated. There were no relevant effects of treatment with etravirine, and the immune response, as measured by IgM production, was not affected by treatment.