


Product Monograph - Etoposide Injection USP
ACTION AND CLINICAL PHARMACOLOGY
Etoposide is a semi-synthetic derivative of podophyllotoxin used in the treatment of certain neoplastic diseases.
In vitro, etoposide has cytostatic action, which prevents the cells from entering mitosis or destroys them in the premitotic phase. Etoposide interferes with the synthesis of DNA and has a secondary effect on arresting cells in resting (G2) phase in experiments with human lymphoblastic cell lines.
Etoposide has a marked action on human hemopoietic cells causing leukopenia and thrombocytopenia. Animal experiments have shown evidence of teratogenicity.
An intravenous dose (259 mg/m2) of tritium-labelled etoposide given over one hour in man, showed the mean volume of distribution to be 32% of body weight. The plasma decay was biphasic with a beta half-life of 11.5 hours. Urinary recovery was 44%, of which 67% was unchanged drug. Recovery in feces was variable (1.5-16%) over a three day period.
In a limited number of children, etoposide administered in a dose of 200-250 mg/m2 produced a peak serum concentration between 17 and 88 mcg/mL and showed a terminal half-life (T½ß) of 5.7 ± 1.3 hours. Mean plasma clearance was 21.5 mL/min/m2 and CSF concentrations 24 hours post-infusion ranged from less than 10 ng/mL to 45 mcg/mL.
After intravenous infusion of etoposide, the Cmax and AUC values exhibit marked intra- and inter- subject variability.
Etoposide crosses the blood brain barrier in low concentrations.
Etoposide is cleared by both renal and non-renal processes, (i.e. metabolism and biliary excretion). Biliary excretion, however, appears to be a minor route of etoposide elimination.
INDICATIONS AND CLINICAL USE
Etoposide Injection USP is indicated as follows:
Small Cell Carcinoma of the Lung
- First-line therapy in combination with other established antineoplastic agents.
- Second-line combination or single agent therapy in patients who have not responded or relapsed on other chemotherapeutic regimens.
Malignant Lymphoma (histiocytic type)
- First-line therapy in combination with other established antineoplastic agents.
Non-small Cell Carcinoma of the Lung
- For patients considered ineligible for surgery, etoposide has been shown effective alone or in combination with cisplatin.
- For patients who require chemotherapy following surgery.
Testicular Malignancies (germ cell tumors including seminomas)
- In combination with other effective chemotherapeutic agents in patients who have already received appropriate therapy.
- In first-line combination chemotherapeutic regimens with appropriate surgical and/or radiotherapeutic procedures.
CONTRAINDICATIONS
Etoposide should not be given to individuals who have demonstrated a previous hypersensitivity to it or any components of the formulation. Also, it is contraindicated in patients having severe leukopenia, thrombocytopenia and severe hepatic and/or renal impairment.
WARNINGS
ETOPOSIDE IS A POTENT DRUG AND SHOULD BE USED ONLY BY QUALIFIED PHYSICIANS EXPERIENCED WITH CANCER CHEMO-THERAPEUTIC DRUGS (SEE WARNINGS AND PRECAUTIONS). BLOOD COUNTS AS WELL AS RENAL AND HEPATIC FUNCTION TESTS SHOULD BE TAKEN REGULARLY. DISCONTINUE THE DRUG IF ABNORMAL DEPRESSION OF BONE MARROW OR ABNORMAL RENAL OR HEPATIC FUNCTION IS SEEN. ETOPOSIDE INJECTION USP CONTAINS POLYSORBATE 80. IN PREMATURE INFANTS A LIFE THREATENING SYNDROME OF LIVER AND RENAL FAILURE, PULMONARY DETERIORATION, THROMBOCYTOPENIA AND ASCITES HAS BEEN ASSOCIATED WITH INJECTABLE VITAMIN E PRODUCT CONTAINING POLYSORBATE 80. ETOPOSIDE INJECTION USP CONTAINS BENZYL ALCOHOL. BENZYL ALCOHOL HAS BEEN ASSOCIATED WITH AN INCREASED INCIDENCE OF NEUROLOGICAL AND OTHER COMPLICATIONS IN NEWBORN INFANTS WHICH ARE SOMETIMES FATAL.
Patients being treated with etoposide must be frequently observed for myelosuppression both during and after therapy. Dose-limiting bone marrow suppression is the most significant toxicity associated with etoposide therapy. Therefore, the following studies should be obtained at the start of therapy and prior to each subsequent dose of etoposide: platelet count, hemoglobin, white blood cell count and differential. The occurrence of a platelet count below 50 000/mm3 or an absolute neutrophil count below 500/mm3 is an indication to withhold further therapy until the blood counts have sufficiently recovered.
Bacterial infection must be brought under control before the administration of etoposide therapy because of the risk of septicemia.
Vaccinations: Concomitant use of etoposide with a live virus vaccine may potentiate the replication of the vaccine virus and/or may increase the adverse reaction of the vaccine virus because normal defense mechanisms may be suppressed by etoposide. Vaccination with a live vaccine in a patient taking etoposide may result in severe infection. Patient's antibody response to vaccines may be decreased. The use of live vaccines should be avoided and individual specialist advice sought (see DRUG INTERACTIONS, Other interactions).
Physicians should be aware of the possible occurrence of an anaphylactic reaction manifested by chills, fever, tachycardia, bronchospasm, dyspnea and/or hypotension (see ADVERSE REACTIONS). Treatment is symptomatic. The administration of etoposide should be terminated immediately, followed by the administration of pressor agents, corticosteroids, antihistamines or volume expanders at the discretion of the physician.
For parenteral administration, etoposide should be given only by slow intravenous infusion (usually over a 30 to 60 minute period) since hypotension has been reported as a possible side effect of rapid intravenous injection.
Pregnancy: Etoposide can cause fetal harm when administered to pregnant women.
Etoposide has been shown to be embryotoxic in rats and teratogenic in mice and rats. There are no adequate and well-controlled studies in pregnant women. If the drug is used during pregnancy, or if the patient becomes pregnant while receiving this drug, the patient should be apprised of the potential hazard to the fetus. Women of childbearing potential should be advised to avoid becoming pregnant.
Given the mutagenic potential of etoposide, an effective contraception is required for both male and female patients during treatment and up to 6 months after ending treatment. Genetic consultation is recommended if the patient wishes to have children after ending the treatment. As etoposide may decrease male fertility, preservation of sperm may be considered for the purpose of later fatherhood.
Etoposide has caused reduced or absent spermatogenesis and reduced testes weights at autopsy in rats and dogs, as well as reduced weight of ovaries in female rats. Chronic toxicity studies in rats have shown etoposide to have an oncogenic potential (see ADVERSE REACTIONS, Hematologic Toxicity).
Nursing Mothers: There has been evidence of etoposide being excreted in human milk.
Because of the potential for serious adverse reactions in nursing infants from etoposide, breast-feeding should be discontinued.
As with any potent antineoplastic drug, the benefit to patient versus the risk of toxicity must be carefully weighed.
PRECAUTIONS
General
The physician must evaluate the need and usefulness of the drug against the risk of adverse reactions. Most such adverse reactions are reversible if detected early. If severe reactions occur, the drug should be reduced in dosage or discontinued and appropriate corrective measures should be taken according to the clinical judgment of the physician. Re-institution of etoposide therapy should be carried out with caution and with adequate consideration of the further need for the drug and alertness to the possible recurrence of toxicity. Patients with low serum albumin may be at increased risk for etoposide-associated toxicities.
Etoposide should be administered by individuals experienced in the use of antineoplastic therapy.
Since leukopenia and thrombocytopenia have been reported in patients on etoposide therapy, platelets and white blood cell counts should be performed prior to each cycle.
A white blood cell count of between 2000-3000 cells/mm3 suggests that the dose of Etoposide should be reduced by 50%. Platelet counts between 75,000 – 100,000 cells/mm3 require a dosage reduction of 50 %. Should the neutrophil count fall below 500 cells/mm3 or the platelet count fall below 50,000 cells/mm3, etoposide should be discontinued and should not be resumed until counts have returned to normal (see WARNINGS).
Neutropenia is at its lowest level seven to fourteen days after initial therapy. Thrombocytopenia is at its lowest level nine to sixteen days after initial therapy. Bone marrow recovery requires 20 days.
Liver and renal function should be regularly monitored.
Professional staff administering Etoposide Injection USP should exercise particular care to prevent spillage and self contact with the drug. Skin reactions, at times severe, associated with accidental exposure to Etoposide Injection USP may occur. Gloves should be worn by anyone handling the drug. If Etoposide Injection USP solution contacts the skin, immediately wash thoroughly with soap and water. If etoposide solution contacts mucous membranes, flush thoroughly with water. Materials used for cleaning accidental spills should be disposed of by incineration.
Carcinogenesis
Carcinogenicity tests with etoposide have not been conducted in laboratory animals. Given its mechanism of action, it should be considered a possible carcinogen in humans.
The occurrence of acute leukemia, which can occur with or without a pre-leukemic phase, has been reported rarely in patients treated with etoposide in association with other antineoplastic drugs. Neither the cumulative risk nor the predisposing factors related to the development of secondary leukemia are known. The roles of both administration schedules and cumulative doses of etoposide have been suggested, but have not been clearly defined.
An 11q23 chromosome abnormality has been observed in some cases of secondary leukemia in patients who have received epipodophyllotoxins. This abnormality has also been seen in patients developing secondary leukemia after being treated with chemotherapy regimens not containing epipodophyllotoxins and in leukemia occurring de novo. Another characteristic that has been associated with secondary leukemia in patients who have received epipodophyllotoxins appears to be a short latency period, with average median time to development of leukemia being approximately 32 months.
DRUG INTERACTIONS
Effects of other drugs on etoposide
Severe cases of neuropathy have been reported in 0.7% of patients possibly due to an interaction of vincristine and etoposide.
Effects of etoposide on other drugs
Concomitant phenytoin therapy is associated with increased etoposide clearance and reduced efficacy. Other antiepileptic therapy may also be associated with increased etoposide clearance and reduced efficacy.
Co-administration of antiepileptic drugs and etoposide can lead to decreased seizure control due to pharmacokinetic interactions between the drugs.
Concomitant warfarin therapy may result in elevated international normalized ratio (INR). Close monitoring of INR is recommended.
Other interactions
Cross resistance between anthracyclines and etoposide has been reported in preclinical experiments.
There is increased risk of fatal systemic vaccine disease with the concomitant use of live vaccines. Live vaccines are not recommended in immunosuppressed patients (see WARNINGS, Vaccinations).
Pediatric Use
Safety and effectiveness in pediatric patients have not been systematically studied. Clinical experience in childhood malignancies is very limited (see WARNINGS).
ADVERSE REACTIONS
The following data on adverse events are based on both oral and intravenous administration of etoposide as a single agent, using several different dose schedules for treatment of a wide variety of malignancies.
Hematologic Toxicity: Since leukopenia and thrombocytopenia have been reported in patients on etoposide therapy, platelets and white blood cell counts should be performed prior to each cycle. A white blood cell count of between 2000 - 3000 cells/mm3 suggests that the dose of etoposide should be reduced by 50%. Platelet counts between 75,000 – 100,000 cells/mm3 require a dosage reduction of 50%. Should the neutrophil count fall below 500 cells/mm3 or the platelet count fall below 50,000 cells/mm3, etoposide should be discontinued and should not be resumed until counts have returned to normal (see WARNINGS).
Myelosuppression is dose related and dose limiting, with granulocyte nadirs occurring 7 to 14 days and platelet nadirs occurring 9 to 16 days after drug administration. Bone marrow recovery is usually complete by day 20, and no cumulative toxicity has been reported.
The occurrence of acute leukemia with or without a preleukemic phase has been reported in patients treated with etoposide in association with other antineoplastic agents.
Gastrointestinal Toxicity: Nausea and vomiting are the major gastrointestinal toxicities. The severity of such nausea and vomiting is generally mild to moderate with treatment discontinuation required in 1% of patients. Gastrointestinal toxicities are slightly more frequent after oral administration than after intravenous infusion. Nausea and vomiting can usually be controlled with standard antiemetic therapy. Mild to severe mucositis/eosophagitis may occur.
Cardiovascular Toxicity: Transient hypotension following rapid intravenous administration has been reported in 1% to 2% of patients. It has not been associated with cardiac toxicity or electrocardiographic changes. No delayed hypotension has been noted. To prevent this occurrence, it is recommended that etoposide be administered by slow intravenous infusion over a 30 to 60 minute period. Hypotension usually responds to cessation of the infusion and/or other supportive therapy as appropriate. When restarting the infusion, a slower administration rate should be used.
Myocardial infarction (some with a fatal outcome) and arrhythmia have been reported.
Allergic Reactions: Anaphylactic-like reactions characterized by chills, fever, tachycardia, bronchospasm, dyspnea and/or hypotension have been reported to occur in 0.7% to 2% of patients during or immediately after etoposide administration. Higher rates of anaphylactic-like reactions have been reported in children who received etoposide infusions at concentrations higher than those recommended. The role that concentration of infusion (or rate of infusion) plays in the development of anaphylactic-like reactions is uncertain. Anaphylactic-like reactions have usually responded promptly to the cessation of infusion of etoposide, and subsequent administration of pressor agents, corticosteroids, antihistamines or volume expanders, as appropriate Acute fatal reactions associated with bronchospasm have been reported. Hypertension and/or flushing and/or seizures have also been reported. Blood pressure usually normalizes within a few hours after cessation of the infusion. Anaphylactic-like reactions can occur with the initial dose of etoposide. Apnea with spontaneous resumption of breathing following discontinuation has been described in patients receiving etoposide infusion.
Alopecia: Reversible alopecia, sometimes progressing to total baldness was observed in up to 66% of patients.
Neurologic Toxicity: Peripheral neuropathy has been reported in 0.7% of patients. The occurrence of Posterior Reversible Encephalopathy Syndrome (PRES) has been reported in patients treated with etoposide in association with other antineoplastic agents.
Other Toxicities: Weakness (3%), mouth ulceration (2%). The following adverse events have been reported in less than 1%: hyperuricemia, sepsis, numbness and tingling, dizziness, depression, nail pigmentation and moniliasis. The following adverse reactions have been rarely reported: interstitial pneumonitis/pulmonary fibrosis, seizures (occasionally associated with allergic reactions), somnolence and fatigue, liver toxicity, fever, aftertaste,Steven Johnson syndrome, toxic epidermal necrolysis (one fatal case has been reported), rash, pigmentation, pruritus, urticaria, constipation, dysphagia, asthenia, malaise, transient cortical blindness, optic neuritis, and radiation recall dermatitis.
Occasionally following extravasation, soft tissue irritation and inflammation has occurred; ulceration is generally not seen.
Metabolic Complications: Tumor lysis syndrome (sometimes fatal) has been reported following the use of etoposide in association with other chemotherapeutic drugs.
The incidences of adverse reactions in Table 1 are derived from multiple databases from studies in patients when etoposide was used either orally or by injection as a single agent.
TABLE 1 - Etoposide – Adverse Reactions
| ADVERSE DRUG EFFECT | RANGE OF REPORTED INCIDENCE (%) |
Hematologic toxicity Leukopenia (less than 1000 WBC/mm3) Leukopenia (less than 4000 WBC/mm3) Thrombocytopenia (less than 50,000 platelets/mm3) Thrombocytopenia (less than 100,000 platelets/mm3) Anemia | 3-17 60-91 1-20 22-41 0-33 |
Gastrointestinal toxicity Nausea and vomiting Abdominal pain Anorexia Diarrhea Stomatitis | 31-43 0-2 10-13 1-13 1-6 |
Other Alopecia Peripheral neurotoxicity Hypotension Allergic reaction Hepatic | 8-66 1-2 1-2 1-2 0-3 |
Legend: WBC=white blood cell
You can report any suspected adverse reactions associated with the use of health products to the Canada Vigilance Program by one of the following 3 ways:
NOTE: Should you require information related to the management of side effects, contact your health professional. The Canada Vigilance Program does not provide medical advice. |
OVERDOSAGE
The anticipated acute complications would be related to etoposide’s hematotoxicity.
Total doses of 2.4 g/m2 to 3.5 g/m2 administered IV over three days resulted in severe mucositis and myelotoxicity.
Metabolic acidosis and cases of serious hepatic toxicity have been reported in patients receiving higher than recommended intravenous doses of etoposide.
There is no known antidote and therefore symptomatic measures should be taken to sustain the patient through any period of toxicity that might occur. Patients’ renal and hepatic functions should be monitored for 3-4 weeks in case of delayed toxicity.
For management of a suspected drug overdose, contact your regional Poison Control Centre.
DOSAGE AND ADMINISTRATION
Note: Plastic devices made of acrylic or ABS (a polymer composed of acrylonitrile, butadiene and styrene) have been reported to crack and leak when used with undiluted
Etoposide Injection USP. This effect has not been reported with diluted Etoposide Injection USP.
Intravenous: 50-100 mg/m2 daily for 5 days.
Hypotension following rapid intravenous administration has been reported, hence, it is recommended that the Etoposide Injection USP solution be administered over a period of not less than 30 minutes (usually over 30 to 60 minutes). Longer infusion times may be required based on patient tolerance. Etoposide Injection USP should not be given by rapid intravenous injection.
Dosage should be modified to take into account the myelosuppressive effects of other drugs in combination therapy or the effects of prior X-ray therapy or chemotherapy which may have compromised the bone marrow reserve.
Preparation of Intravenous Solutions
Etoposide Injection USP MUST BE DILUTED PRIOR TO USE with either 5% dextrose injection USP or 0.9% sodium chloride injection USP to give a final concentration of 0.2 or 0.4 mg/mL. It is recommended that the product be used immediately after reconstitution.
MORE CONCENTRATED SOLUTIONS SHOW CRYSTAL FORMATION UPON STIRRING OR SEEDING WITHIN 5 MINUTES AND SHOULD NOT BE GIVEN INTRAVENOUSLY.
Etoposide Injection USP diluted to 0.4 mg/mL and administered through tubing connected to a pump with peristaltic mechanism may precipitate out of solution in the tubing. Contact with buffered aqueous solutions above pH 8 should be avoided. Reconstitution results in a clear, colourless solution.
Etoposide Injection USP diluted with 0.9% sodium chloride injection USP or 5% dextrose injection USP to a concentration of 0.2 mg/mL is stable for 7 days in polyvinyl chloride (PVC) bags, at 2ºC to 8ºC and at room temperature between 15ºC to 30ºC.
Etoposide Injection USP diluted with 0.9% sodium chloride injection USP or 5% dextrose injection USP to a concentration of 0.4 mg/mL is stable for 12 hours in polyvinyl chloride (PVC) bags, at 2ºC to 8ºC and at room temperature between 15ºC to 30ºC.
Etoposide Injection USP should not be mixed with other antineoplastic drugs. Care should be taken to prevent spillage and self contact with the drug. If Etoposide Injection USP solution contacts the skin, immediately wash thoroughly with soap and water. If Etoposide Injection USP solution contacts mucous membranes, flush thoroughly with water.
PHARMACEUTICAL INFORMATION
Drug Substance
Proper Name: Etoposide
Chemical Name: (1) Furo[3',4':6,7]naphtho[2,3-d]-1,3-dioxol-6(5aH)-one,9-[(4,6-0-ethylidene-β-D-glucopyranosyl)oxyl]5,8,8a,9-tetrahydro-5-(4-hydroxy-3,5-dimethoxyphenyl), [5R-[5α,5aβ,-8aα,9β(R*)]]-;
(2) 4'-Demethylepipodophyllotoxin 9-[4-6-0-(R)-ethylidene-β-D-glucopyranoside].
Structural formula:
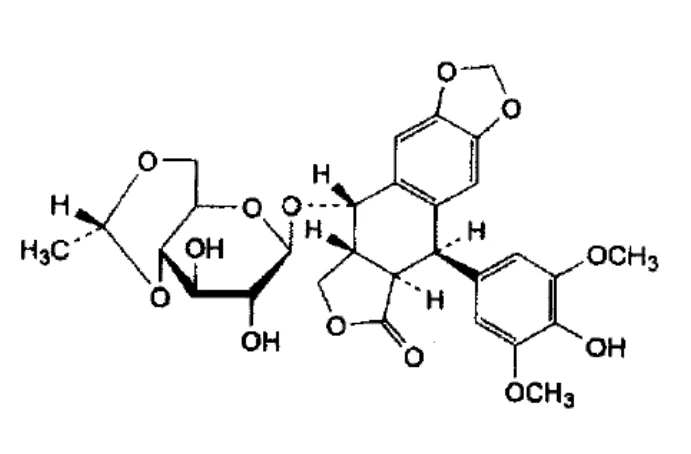
Molecular Formula and molecular mass: C29H32O13, 588.6 g/mol.
Physicochemical properties: Etoposide is a white to almost white crystalline powder. Etoposide is a semi-synthetic derivative of podophyllotoxin. It is sparingly soluble in methanol, slightly soluble in alcohol and in methylene chloride.
Preparation for Intravenous Administration
Etoposide Injection USP MUST BE DILUTED PRIOR TO USE with either 5% dextrose injection USP or 0.9% sodium chloride injection USP to give a final concentration of 0.2 mg/mL or 0.4 mg/mL. It is recommended that the product be used immediately after reconstitution.
As with all parenteral drug products, intravenous admixtures should be inspected visually for clarity, particulate matter, precipitate, discoloration and leakage prior to administration, whenever solution and container permit. Solutions showing haziness, particulate matter, precipitate, discoloration or leakage should not be used.
STORAGE AND STABILITY
Etoposide Injection USP should be stored at room temperature (15-30°C) and protected from light. Once multidose vial is punctured, Etoposide Injection USP should be protected from light and stored between 15-30 °C and used within 28 days.
Etoposide Injection USP diluted with 0.9% sodium chloride injection USP or 5% dextrose injection USP to a concentration of 0.2 mg/mL is stable for 7 days in polyvinyl chloride (PVC) bags, at 2ºC to 8ºC and at room temperature between 15ºC to 30ºC.
Etoposide Injection USP diluted with 0.9% sodium chloride injection USP or 5% dextrose injection USP to a concentration of 0.4 mg/mL is stable for 12 hours in polyvinyl chloride (PVC) bags, at 2ºC to 8ºC and at room temperature between 15ºC to 30ºC.
SPECIAL INSTRUCTIONS FOR HANDLING OF CYTOTOXIC DRUGS
Handling and Disposal:
- 1. Preparation of Etoposide Injection USP should be done in a vertical laminar flow hood (Biological Safety Cabinet – Class II).
- 2. Personnel preparing Etoposide Injection USP should wear PVC gloves, safety glasses, disposable gowns and masks.
- 3. All needles, syringes, vials and other materials which have come in contact with Etoposide Injection USP should be segregated and incinerated at 1000°C or more. Sealed containers may explode if a tight seal exists. Intact vials should be returned to the manufacturer for destruction. Proper precautions should be taken in packaging these materials for transport.
- 4. Personnel regularly involved in the preparation and handling of etoposide should have bi-annual blood examinations.
DOSAGE FORMS, COMPOSITION AND PACKAGING
Each mL contains 20 mg etoposide, benzyl alcohol (as preservative), anhydrous citric acid, ethanol, polyethylene glycol, and polysorbate 80.
Etoposide Injection USP 20 mg/mL is available in multi-dose vials of 100 mg (5 mL), 200 mg (10 mL), 500 mg (25 mL), and 1 g (50 mL) of etoposide at a concentration of 20 mg/mL.
HUMAN PHARMACOLOGY
Pharmacokinetics
On intravenous administration, the disposition of etoposide is best described as a biphasic process with a distribution half-life of about 1.5 hours and terminal elimination half-life ranging from 4 to 11 hours. Total body clearance values range from 33 to 48 mL/min or 16 to 36 mL/min/m2 and, like the terminal elimination half-life, are independent of dose over a range 100-600 mg/m2. Over the same dose range, the areas under the plasma concentration vs. time curves (AUC) and the maximum plasma concentration (Cmax) values increase linearly with dose. Etoposide does not accumulate in the plasma following daily administration of 100 mg/m2 for 4 to 5 days.
The mean volumes of distribution at steady state fall in the range of 18 to 29 litres or 7 to 17 L/m2. Etoposide enters the CSF poorly. Although it is detectable in CSF and intracerebral tumours, the concentrations are lower than in extracerebral tumours and in plasma. Etoposide concentrations are higher in normal lung than in lung metastases and are similar in primary tumours and normal tissues of the myometrium.
In vitro, etoposide is highly protein bound (97%) to human plasma proteins. In a study of the effects of other therapeutic agents on in vitro binding of 14C etoposide to human serum proteins, only phenylbutazone, sodium salicylate, and aspirin displace protein-bound etoposide at concentrations achieved in vivo.
After intravenous administration of 3H-etoposide (70-290 mg/m2), mean recoveries of radioactivity in the urine range from 42 to 67%, and fecal recoveries range from 0 to 16% of the dose. Less than 50% of an intravenous dose is excreted in the urine as etoposide with mean recoveries of 8 to 35% within 24 hours.
In children, approximately 55% of the dose is excreted in the urine as etoposide in 24 hours. The mean renal clearance of etoposide is 7 to 10 mL/min/m2 or about 35% of the total body clearance over a dose range of 80 to 600 mg/m2. An inverse relationship between plasma albumin levels and etoposide renal clearance is found in children.
Etoposide, therefore, is cleared by both renal and nonrenal processes, i.e. metabolism and biliary excretion. The effect of renal disease on plasma etoposide clearance is not known in children.
Biliary excretion of unchanged drug and/or metabolites is an important route of etoposide elimination as fecal recovery of radioactivity is 44% of the intravenous dose. Only 6% or less of an intravenous dose is recovered in the bile as etoposide. Metabolism accounts for most of the nonrenal clearance of etoposide. The major urinary metabolite of etoposide in adults and children is the hydroxy acid [4'-demethyl epipodophyllic acid-9-(4, 6-0-(R)-ethylidene-β-D-glucopyranoside)], formed by opening of the lactone ring. It is also present in human plasma, presumable as the trans isomer. Glucuronide and/or sulfate conjugates of etoposide are excreted in human urine and represent 5 to 22% of the dose.
After intravenous infusion, the Cmax and AUC values exhibit marked intra- and inter-subject variability.
In adults, the total body clearance of etoposide is correlated with creatinine clearance, low serum albumin concentration, and nonrenal clearance. In adult cancer patients with liver dysfunction, total body clearance of etoposide is not reduced. Patients with impaired renal function receiving etoposide have exhibited reduced total body clearance, increased AUC and higher steady state volume of distribution (see DOSAGE AND ADMINISTRATION). Concomitant cisplatin therapy is associated with reduced total body clearance of etoposide. In children, elevated SGPT levels are associated with reduced drug total body clearance. Prior use of cisplatin may also result in a decrease of etoposide total body clearance in children.
Although minor differences in pharmacokinetic parameters between gender and between patients ≤ 65 years and > 65 years have been observed, these are not considered clinically significant.
ANIMAL PHARMACOLOGY
In vitro
Etoposide interferes with the synthesis of DNA. In vitro experiments with radiolabelled thymidine have demonstrated that etoposide has a concentration dependent inhibition of thymidine uptake.
It has been shown that etoposide, in vitro tests on chick connective tissue (fibroblasts) arrested mitosis at metaphase. These effects appeared to be concentration dependent.
Etoposide will inhibit tissue culture in vitro as shown in studies with cell line of P-815, HeLa and L types.
Human hemopoietic cell lines treated with etoposide showed a high incidence of multiple chromosomal abnormalities.
The drug has shown activity in rodent transplantable tumors of the sarcomas 37 and 180 and the Walker carcinosarcoma, as well as leukemias P-1534 and L-1210.
Etoposide has been shown to cause metaphase arrest in chick fibroblasts. Its main effect, however, appears to be at the late S or early G2 portion of the cell cycle in mammalian cells. Two different dose-dependent responses are seen. At high concentrations (10 mcg/mL or more), lysis of cells entering mitosis is observed. At low concentrations (0.3 to 10 mcg/mL), cells are inhibited from entering prophase. It does not interfere with microtubular assembly. The predominant macromolecular effect of etoposide appears to be the induction of DNA strand breaks by an interaction with DNA-topoisomerase II or the formation of free radicals.
Pharmacokinetics
In rats, etoposide was distributed in highest concentrations in liver, kidney and small intestine thirty minutes after intravenous injection of radio-labelled etoposide. Etoposide accumulated to a significant degree after 24 hours in liver, kidney, bile and thyroid, and its major route of excretion was shown to be the bile.
In monkeys, following oral administration, a maximum blood level of etoposide was achieved after 45 minutes and following an intravenous bolus administration, a maximum level was seen after 15 minutes.
In monkeys, the oral half life was 1.7 hours, and the intravenous half life was 1.3 hours. Nineteen percent of the etoposide oral dose was excreted in the urine after 80 hours, and 63% of etoposide oral dose was found in the feces.
TOXICOLOGY
Acute Toxicity
The LD50 was determined in mice, rats and rabbits (Table 2).
TABLE 2 - LD50 of etoposide IV
| Etoposide solution | Ampoule solvent | |||||||
| mg/kg | mL/kg | mL/kg | ||||||
Mouse Rat Rabbit | 118 ± 9.5 68 ± 3.5 80 | 5.9 3.4 4.0 | 6.6 ± 0.3 4.2 ± 0.4 ca 4.0 | |||||
The exact estimate of the toxicity of etoposide is limited by the toxicity of the solvent, so acute intravenous toxicity of etoposide cannot be given with certainty.
Subacute Toxicity
Etoposide was administered intraperitoneally at doses of 0.6, 1.8 and 6.0 mg/kg/day to three groups of 20 rats (10 males and 10 females) for four weeks.
At 0.6 mg/kg/day
Produced no significant effects. No deaths occurred.
At 1.8 mg/kg/day
Produced anemia and transient lymphopenia with significant thymus involution and reduced splenic lymphoid tissue in some animals. No deaths occurred.
At 6.0 mg/kg/day
Significant effects on the hemopoietic and lymphopoietic systems, characterized by fairly severe anemia and marked leukopenia with agranulocytosis in one case. Spermiogenesis in the males was diminished or absent. Non-specific effects (weight loss, diarrhea, pulmonary lesions, hepatocyte degeneration) were reported. Mortality was 2/20 in this group.
At 0.6 mg/kg/day at necropsy showed slight evidence of thymus involution in 11/20 rats. There were marked areas of retroperitoneal hemorrhage and small petechial hemorrhages in the pleura and renal capsule.
At 1.8 mg/kg/day at necropsy showed moderate thymus involution in 18/20 rats. There was a small quantity of serosanguinous ascitic fluid in 7/20 rats. Also seen were small petechial hemorrhages in pleura and renal capsule as in other dosage groups.
At 6.0 mg/kg/day at necropsy resulted in two spontaneous deaths, one with no postmortem changes, the other with hemorrhagic peritonitis due to perforation. At necropsy significant thymus involution was seen in three, with obvious involution in the remainder. The liver appeared swollen and edematous in 10/18 rats.
Petechial hemorrhages in lungs and renal capsule were observed.
Etoposide was administered intravenously at dosage levels of 0.4, 1.2 and 3.6 mg/kg/day to three groups of four rhesus monkeys (two males and two females) for four weeks.
At 0.4 mg/kg/day
Was without any significant effect.
At 1.2 mg/kg/day
Produced non-significant anemia and leukopenia and diminished lymphoid tissue.
At 3.6 mg/kg/day
Produced progressive anemia and severe leukopenia and agranulocytosis and impaired platelet function (plasma clot retraction). There was diminished lymphoid tissue and reaction centres in the spleen and lymph nodes in all four monkeys and evidence of focal hepatocyte degeneration. Non-specific effects at this dosage included weight loss, reduced serum albumin, mild enteritis and increased hemosiderin deposition in one or two animals. Mortality was zero in all groups.
At 0.4 mg/kg/day at necropsy showed small grey/yellow nodules in the lungs of two monkeys. At 1.2 mg/kg/day showed small grey/yellow nodules in the lungs of one monkey, and in another the liver was congested with small surface scars.
At 3.6 mg/kg/day at necropsy showed findings of enlarged submandibular glands, small lung abscesses, grey nodules, small hemorrhagic foci, enlarged mesenteric lymph nodes and fatty bone marrow.
The veins showed no evidence of poor local tolerance.
Chronic Toxicity
Three groups of 80 rats (40 males and 40 females) were given etoposide ampoule solution orally for 26 weeks at 3, 10 and 30 mg/kg daily. Following the completion of the 26 week study, 40 rats at the mid and high dose level received no drug orally for an additional eight weeks to detect possible reversibility of effects.
At 3 mg/kg
Females had a decrease in leukocytes. Both females and males had decreases in RBC, erythropoiesis, leukopoiesis and increased serum cholesterol.
At 10 mg/kg
Decreased total leukocytes, lymphocytes and monocytes, plasma cell increase, bone marrow changes showing moderate disturbance of erythropoiesis and leukopoiesis.
At 30 mg/kg
Females had increased platelet counts. Males had diarrhea. Both females and males had impaired food intake and weight gain, decreased leukocytes, lymphocytes, monocytes, neutrophils and anemia due to changes in the bone marrow. Serum cholesterol was increased. Urine volume was increased with enhanced electrolyte excretion.
At necropsy, the following changes were noted - reduced weight of testes, ovary and spleen; increased liver weights; thymus involution; a mammary adenocarcinoma and nephroblastoma; degenerative changes in seminal epithelium. These immunosuppressive effects on the hemopoietic and lymphatic system were reversible following treatment, however, histological lung changes were more pronounced after the recovery phase. The tumor findings can be related to the cytostatic mechanism.
Three groups of six beagle dogs (three males and three females) were given etoposide ampoule solution for 26 weeks orally at 0.5, 1.5 and 5-6 mg/kg once daily. Following the completion of the 26 week study, two dogs each of the mid and high dose level were kept for a further five weeks without drug administration to demonstrate reversibility of effects. The following toxicity was reported:
At 0.5 mg/kg
Changes in bone marrow, slight disturbances of erythropoiesis, sporadic occurrence of micronuclei in normoblasts and leukocytes, increased urinary excretion of potassium.
At 1.5 mg/kg
Increased platelet counts, disturbed erythropoiesis and leukopoiesis, ECG changes.
Three males showed decreased testicular weights and reduced spermiogenesis.
At 5-6 mg/kg
Reduction in body weight gain, food intake impaired, loss of weight, black pigmentation of ear skin due to melanin deposition in basal cells of epidermis. Hematological findings showed a decrease in total leukocyte counts, neutrophils, lymphocytes and monocytes and a slight decrease in erythrocytes, hematocrit and hemoglobin. Also macrocytosis, hypochromic anemia and micronuclei in the erythrocytes and leukocytes, bone marrow changes, and increased platelet count were noted. Also a marked transient increase of SGPT values and a slight trend to increased BUN and creatinine values together with a decrease in blood protein were observed.
The immunosuppressive effects on the hematopoietic and lymphatic system were reversible following withdrawal of treatment.
In summary, the results of the two oral 26-week toxicity studies revealed clear-cut toxic effects after oral administration of high doses of the ampoule solution of etoposide in rats and dogs. The main evidence of toxicity was seen in the erythro and leukopoietic organs, thymus and testes.
Hemolysis Studies
Etoposide given in a four-week intravenous study in monkeys produced no evidence of intravascular hemolysis. Plasma protein precipitation studies in vivo and in vitro indicate that intravenous administration of etoposide ampoule solution should have no untoward effects on human blood and plasma at the doses likely to be used.
Teratology
Etoposide was subjected to a teratology study in SPF rats at doses of 0.13, 0.4, 1.2 and 3.6 mg/kg/day administered intravenously on days 6 to 15 of gestation. Etoposide caused dose-related maternal toxicity, embryotoxicity and teratogenicity at dose levels of 0.4 mg/kg/day and higher. Embryonic resorptions were 90 and 100 percent at the two highest dosages. At 0.4 and 1.2 mg/kg, fetal weights were decreased and fetal abnormalities occurred including major skeletal abnormalities, exencephaly, encephalocele and anophthalmia. At the dose of 1.2 mg/kg, a prenatal mortality of 92 percent was observed with 50 percent of the implanting fetuses abnormal. Even at the lowest dose tested, 0.13 mg/kg, a significant increase in retarded ossification was observed.
A study of Swiss-Albino mice given a single intraperitoneal injection of etoposide at dosages of 1.0, 1.5 and 2 mg/kg on days 6, 7 and 8 of gestation disclosed dose-related embryotoxicity, various cranial abnormalities, major skeletal malformations, an increased incidence of intrauterine death and significantly decreased average fetal body weights. Maternal weight gain was not affected.
Etoposide induced aberrations in chromosome number and structure in embryonic murine cells.
REFERENCES
- 1. Aisner J, Lee EJ. Etoposide: Current and future status. Cancer 1991; 67 (Suppl.1): 215-219.
- 2. Alade SL, Brown RE, Paquet A. Polysorbate 80 and E-ferol toxicity. Pediatrics 1986; 77 (4): 593-597.
- 3. Blume KG, Forman SJ, O'Donnell MR, et al. Total body irradiation and high-dose etoposide: A new preparatory regimen for bone marrow transplantation in patients with advanced hematologic malignancies. Blood 1987; 69: 1015-1020.
- 4. Dorr RT. Antidotes to vesicant chemotherapy extravasations. Blood Reviews 1990; 4: 41-60.
- 5. Fleming RA, Miller AA and Stewart CF. Etoposide: An update Clinical Pharmacy 1989; 8: 274-293.
- 6. Gaver RC, Deeb G. The effect of other drugs on the in vitro binding of 14C-etoposide to human serum proteins. Proc Am Assn Cancer Res 1989;.30: 536 (abs 2132).
- 7. Harvey VJ, Slevin ML, Joel SP, Johnston A and Wrigley PFM. The effect of food and concurrent chemotherapy on the bioavailability of oral etoposide. Br J Cancer 1985; 52: 363-7.
- 8. Hecker JF. Survival of intravenous chemotherapy infusion sites. Brit J Cancer 1990; 62: 660-662.
- 9. Henwood JM and Brogden RN. Etoposide. A review of its pharmacodynamic and pharmacokinetic properties, and therapeutic potential in combination chemotherapy of cancer. Drugs 1990; 39(3): 438-490.
- 10. Johnson DH, Greco FA, Wolff SN. Etoposide-induced hepatic injury: A potential complication of high-dose therapy. Cancer Treat Rep 1983; 67: 1023-1024.
- 11. Luikart SD, Propert KJ, Modeas CR, et al. High-dose etoposide therapy for extensive small cell lung cancer: A Cancer and Leukemia Group B study. Cancer Treat Rep 1987; 71: 533-534.
- 12. Pedersen-Bjergaard J, Daugaard G, Hansen SW, et al. Increased risk of myelodysplasia and leukemia after etoposide, cisplatin, and bleomycin for germ-cell tumours. Lancet 1991; 338: 359-363.
- 13. Piazza E, Cattaneo MT and Varini M. Pharmacokinetic studies in lung cancer in patients. Cancer 1984; 54: 1187-1192.
- 14. Postmus PE, Mulder NH, Sleijfer DT. High-dose etoposide for refractory malignancies: A phase I study. Cancer Treat Rep 1984; 68: 1471-1474.
- 15. Slevin ML. The clinical pharmacology of etoposide. Cancer 1991;67 (Suppl 1): 319-329.
- 16. Stewart CF, Arbuck SG, Fleming RA, et al. Changes in the clearance of total and unbound etoposide in patients with liver dysfunction. J Clin Oncol 1990; 8: 1874-1879.
- 17. Van Echo DA, Wiernik PH, Aisner J. High-dose VP-16-213 (NSC 141540) for the treatment of patients with previously treated acute leukemia. Cancer Clin Trials 1980; 3: 325-328.
- 18. Van Maanen JMS, Retel J, de Vries J, et al. Mechanism of action of antitumor drug etoposide: A review. J Natl Cancer Inst 1988; 80: 1526-1533.
- 19. Wolff SN, Fer MF, McKay CM, et al. High-dose VP-16-213 and autologous bone marrow transplantation for refractory malignancies: A phase I study. J Clin Oncol 1983; 1: 701-705.
Small Cell Lung Cancer
- 20. Banham S, Dorward A, Hutcheon A, Ahmedzai S, Cunningham D, Burnett A, Soukop M, Lucie N and Kaye S. The role of VP-16 in the treatment of small-cell lung cancer: Studies of the west of Scotland cancer group. Seminars in Oncology 1985; 12: 2-6.
- 21. Cunningham D, Banham SW, Hutcheon AH, Dorward A, Ahmedzai S, Tansey P, Soukop M, Stevenson RD, Stack BR, Kaye SB, Lucie N and Burnett AK. High-dose cyclophosphamide and VP 16 as late dosage intensification therapy for small cell carcinoma of lung. Cancer Chemother Pharmacol 1985; 15: 303-6.
- 22. Evans WK, Osoba D, Feld R, Shepherd FA, Bazos MJ and DeBoer G. Etoposide (VP-16) and Cisplatin: An effective treatment for relapse in small-cell lung cancer. J Clin Oncol 1985; 3: 65-71.
- 23. Feld R, Evans WK, DeBoer G, Quirt IC, Shepherd Fa, Yeoh JL, Pringle JF, Payne DG, Herman JG, Chamberlain D, Brown TC, Baker MA, Myers R, Blackstein ME and Pritchard KI. Combined modality induction therapy without maintenance chemotherapy for small cell carcinoma of the lung. J Clin Oncol 1984; 2: 294-304.
- 24. Greco FA, Johnson DH, Hande KR, Porter LL, Hainsworth JD and Wolff SN. High dose etoposide (VP-16) in small-cell lung cancer. Seminars in Oncology 1985; 12: 42-4.
- 25. Johnson DH, Greco Fa, Strupp J, Hande K and Hainsworth D. Prolonged administration of oral etoposide in patients with relapsed or refractory small-cell lung cancer: A phase II trial. Journal of Clinical Oncology 1990; 8 (10) October: 1613-1617.
- 26. Johnson DH, Hainsworth JD, Hande KR and Greco FA. Current status of etoposide in the management of small cell lung cancer. Cancer 1991; 67 (1 Suppl.): 231-244.
- 27. Johnson DH, Keller JH, Kallas GJ, DeConti RC et al. A randomized trial to compare intravenous and oral etoposide in combination with cisplatin for the treatment of small cell lung cancer. Cancer 1991; 67 (1 Suppl.): 245-249.
- 28. Johnson DH, Wolff SN, Hainsworth JD, Porter LL, Grosh WW, Hande KR and Greco FA. Extensive-stage small-cell bronchogenic carcinoma: Intensive induction chemotherapy with high-dose cyclophosphamide plus high-dose etoposide. J Clin Oncol 1985; 3: 170-5.
- 29. Klastersky J, Sculier JP, Dumont JP, Becquart D, Vandermoten G, Rocmans P, Michel J, Longeval E and Dalesio O. Combination chemotherapy with adriamycin, etoposide, and cylcophosphamide for small cell carcinoma of the lung. Cancer 1985; 56: 71-5.
- 30. Littlewood TJ, Smith AP, Anderson G, Chappell AG and James KW. Cisplatin and etoposide alternating with vincristine, doxorubicin and cyclophosphamide in patients with small cell lung cancer. Eur J Respir Dis 1985; 67: 294-300.
- 31. Livingston RB, Mira JG, Chen TT, McGavran M, Costanzi JJ and Samson M. Combined modality treatment of extensive small cell lung cancer: A southwest oncology group study. J Clin Oncol 1984; 2: 585-90.
- 32. Lowenbraun S, Birch R, Buchanan R, Krauss S, Durant J, Perez C, Mill W, Vollmer R, Ogden L and the Southeastern Cancer Study Group. Combination chemotherapy in small cell lung carcinoma. Cancer 1984; 54: 2344-50.
- 33. Matelski, HW, Lokich JJ, Huberman MS, Zipoli TE, Paul S, Sonneborn H and Philips D. Adriamycin, cyclophosphamide, and etoposide (VP-16-213) in extensive-stage small cell lung cancer. Am J Clin Oncol 1984; 7: 729-32.
- 34. Murray N, Shah A, Wilson K, Goldie J, Voss N, Fryer C, Klimo P, Coy P, Hadzic E, Gudauskas G and Fowler R. Cyclic alternating chemotherapy for small cell carcinoma of the lung. Cancer Treat Rep 1985; 69: 1241-2.
- 35. Natale RB, Shank B, Hilaris BS and Wittes RE. Combination cyclophosphamide, adriamycin, and vincristine rapidly alternating with combination cisplatin and VP-16 in treatment of small cell lung cancer. Am J Med 1985; 78: 303-8.
- 36. Natale RB and Wittes RE. Alternating combination chemotherapy regimens in small-cell lung cancer. Seminars in Oncology 1985; 12: 7-13.
- 37. Reddy, SK, Takita H, Lane WW, Vincent RG, Chen TY, Caracandas JE and Regal A-M. Cyclic alternating combination chemotherapy for small cell lung cancer. Cancer Chemother Pharmacol 1984; 12: 190-3.
- 38. Sculier JP, Klastersky J, Stryckmans P and the EORTC Lung Cancer Working Party (Belgium). Late intensification in small-cell lung cancer: A phase I study of high doses of cyclophosphamide and etoposide with autologous bone marrow transplantation. J Clin Oncol 1985; 3: 184-91.
- 39. Spitzer G, Farha P, Valdivieso M, Dicke K, Zander A, Vellekoop L, Murphy WK, Dhingra HM, Umsawasdi T, Chiuten D and Carr DT. High-dose intensification therapy with autologous bone marrow support for limited small-cell bronchogenic carcinoma. J Clin Oncol 1986; 4: 4-13.
- 40. Steward WP, Thatcher N, Edmundson JM, Shiu W and Wilkinson PM. Etoposide infusions for treatment of metastatic lung cancer. Cancer Treat Rep 1984; 68: 897-9.
- 41. Thatcher N, Stout R, Smith DB, Grotte G, Winson M, Bassett H and Carroll KB (From the Manchester Lung Tumour Group). Three months treatment with chemotherapy and radiotherapy for small cell lung cancer. Br J Cancer 1985; 52: 327-32.
- 42. Timothy AR, Calman FMB, Bateman NT, Farebrother M, Slevin ML, Bellamy D, Rubens RD and Costello J. Single-dose etoposide in combination with vincristine and doxorubicin in the treatment of small-cell lung cancer (SCLC). Seminars in Oncology 1985; 12: 45-7.
Non-Small Cell Lung Cancer
- 43. Albain KS. Bitran JD, Golomb HM, Hoffman PC, DeMeester TR, Skosey C, Noble S and Blough RR. Trial vindesine, etoposide and cisplatin in patients with previously treated, advanced-stage, non-small cell bronchogenic carcinoma. Cancer Treat Rep 1984; 68: 413-5.
- 44. Anderson G and Payne H. Response rate and toxicity of etoposide (VP-16) in squamous carcinoma of the lung: Report from the lung cancer treatment study group. Seminars in Oncology 1985; 12: 21-2.
- 45. Bertrand M, Multhauf P, Presant C, Rappaport D, Blayney DW, Carr BI, Cecchi G, Doroshow JH, Emont E, Goldberg D, Kogut N, Leong L and Margolin K. Phase II trial of etoposide, vincristine and high dose cisplatin in advanced non-small cell lung cancer. Cancer Treat Rep 1985; 69: 1335-6.
- 46. Bitran JD, Golomb HM, Hoffman PC, Albain K, Evans R, Little AG, Purl S and Skosey C. Protochemotherapy in non-small cell lung carcinoma. An attempt to increase surgical resectability and survival. A preliminary report. Cancer 1986; 57: 44-53.
- 47. Bonomi P. Recent advances in etoposide for non-small cell lung cancer. Cancer 1991; 67 (1 Suppl.): 254-259.
- 48. Joss RA, Alberto P, Obrecht JP, Barrelet L, Hodener EE, Siegenthaler P, Goldhirsch A, Mermillod B and Cavalli F. Combination chemotherapy for non-small lung cancer with doxorubicin and mitomycin or cisplatin and etoposide. Cancer Treat Rep 1984; 68: 1079-84.
- 49. Klastersky J. VP-16 and cisplatin in the treatment of non-small-cell lung cancer. Seminars in Oncology 1985; 12: 17-20.
- 50. Mitrou PS, Graubner M, Berdel WE, Mende S, Gropp C, Diehl V and Klippstein TH. Cis-platinum (DDP) and VP16-213 (etoposide) combination chemotherapy for advanced non-small cell lung cancer. A phase II clinical trial. Eur J Cancer Clin Oncol 1984; 20: 347-51.
- 51. Osaba D, Rusthoven JJ, Turnbull KA, Evans WK and Shepherd FA. Combination chemotherapy with bleomycin, etoposide and cisplatin in metastic non-small-cell lung cancer. J Clin Oncol 1985; 3: 1478-85.
- 52. Ruckdeschel JC. Etoposide in the management of non-small cell lung cancer 1991; 67: 250-253.
- 53. Scagliotti GV, Lodico D, Gozzelino F, Bardessono F, Albera C, Gatti E and Pescetti G. Unresectable non-small cell lung cancer chemotherapy with high-dose cisplatin and etoposide. Oncology 1985; 42: 224-8.
- 54. Wils JA, Utama I, Naus A and Verschueren TA. Phase II randomized trial of radiotherapy alone vs the sequential use of chemotherapy and radiotherapy in stage III non-small cell lung cancer. Phase II Trial of chemotherapy alone in stage IV non-small cell lung cancer. Eur J Cancer Clin Oncol 1984; 20: 911-4.
Malignant Lymphoma
- 55. Gasser AB, Steward WP, Wagstaff J, Scarffe JH and Crowther D. Treatment of relapsed non-Hodgkin's lymphoma with a combination of hydroxyurea, ifosfamide and etoposide. Cancer Treat Rep 1985; 69: 225-6.
- 56. Hagberg H, Cavallin-Stahl E and Lind J. Ifosfamide and etoposide as salvage therapy for non-Hodgkin's lymphoma. Scan J Haematol 1986; 36: 61-4.
- 57. Hancock BW. Vindesine, etoposide (VP-16), and Prednisolone (VEP) in relapsed patients with grade II non-Hodgkin's lymphoma. Seminars in Oncology 1985; 12: 26-8.
- 58. Judson IR and Wiltshaw E. Cis-dichlorodiammineplatinum (cis-platinum) and etoposide (VP-16) in malignant lymphoma - an effective salvage regimen. Cancer Chemother Pharmacol 1985; 14: 258-61.
- 59. O'Reilly SE, Klimo P and Connors JM. The evolving role of etoposide in the management of lymphomas and Hogkin's disease. Cancer 1991; 67 (1 Suppl.): 271-280.
Testicular Malignancies
- 60. Brindley CJ, Antoniw P, Newlands ES and Bagshawe KD. Pharmacokinetics and toxicity of the epipodophyllotoxin derivative etoposide (VP16-213) in patients with gestational choriocarcinoma and malignant teratoma. Cancer Chemother Pharmacol 1985; 15: 66-71.
- 61. Hainsworth JD, Williams SD, Einhorn LH, Birch R and Greco FA. Successful treatment of resistant germinal neoplasms with VP-16 and cisplatin: Results of a southeastern cancer study group trial. J Clin Oncol 1985; 3: 666-71.
- 62. Loehrer Sr PJ. Etoposide therapy for testicular cancer. Cancer 1991; 67 (1 Suppl.): 220-224.
- 63. Loehrer Sr PJ, Einhorn LH and Williams SD. VP-16 plus ifosfamide plus cisplatin as salvage therapy in refractory germ cell cancer. J Clin Oncol 1986; 4: 528-36.
- 64. Pizzocaro Giorgio, Pasi M, Salvioni R, Zanoni F, Milani A and Piva L. Cisplatin and etoposide salvage therapy and resection of the residual tumor in pretreated germ cell testicular cancer. Cancer 1985; 56: 2399-2403.
- 65. Pizzocaro G, Piva L, Salvioni R, Zanoni F and Milani A. Cisplatin, etoposide, bleomycin first-line therapy and early resection of residual tumor in far-advanced germinal testis cancer. Cancer 1985; 56: 2411-5.
- 66. Srougi M, Simon SD and Menezes de Goes G. Vinblastine, actinomycin D, bleomycin, cyclophosphamide and cis-platinum for advanced germ cell testis tumors: Brazilian experience. The Journal of Urology 1985; 134: 65-9.
- 67. Taylor RE, Duncan W, Davey P, Munro Ai and Cornbleet MA. Cisplatin combination chemotherapy for advanced germ-cell testicular tumours. British Journal of Urology 1985; 57: 567-73.
- 68. Williams SD, Birch R, Einhorn LH, et al. Treatment of disseminated germ-cell tumors with cisplatin, bleomycin, and either vinblastine or etoposide. N Engl J Med 1987; 316: 1435-1440.
- 69. Bristol Laboratories of Canada, Product Monograph for Vepesid, (Etoposide; 20 mg/ml Injection and 50 mg capsules), Control Number: 28496, Date of Revision: December 2nd, 1994.
- 70. Bristol-Myers Squibb Canada, Product Monograph for Vepesid, (Etoposide; 50 mg capsules), Control Number: 179914, Date of Revision: March 3, 2015.
- 71. Hospira Healthcare Corporation, Prescribing Information for Etoposide Injection USP (20 mg/ml; 100 mg/ml, 200 mg/ml, 1g/50 ml), Control Number: 114553, Date of Preparation: June 6th, 2007.