


Product Monograph - GD-Azithromycin
SUMMARY PRODUCT INFORMATION
| Route of Administration | Dosage Form / Strength | Clinically Relevant Nonmedicinal Ingredients For a complete listing see DOSAGE FORMS, COMPOSITION AND PACKAGING |
| Oral | Tablet, 250 mg azithromycin (as azithromycin dihydrate) | pregelatinized starch, sodium croscarmellose, sodium lauryl sulphate and lactose |
Powder for oral suspension, azithromycin 100 mg/5 mL, 200 mg/5 mL when reconstituted (as azithromycin dihydrate) | sucrose and sodium phosphate |
INDICATIONS AND CLINICAL USE
GD-AZITHROMYCIN for Oral Administration
GD-AZITHROMYCIN (azithromycin dihydrate) for oral administration is indicated for treatment of mild to moderate infections caused by susceptible strains of the designated microorganisms in the following diseases and specific conditions. As recommended dosages, durations of therapy and applicable patient populations vary among these infections, see DOSAGE AND ADMINISTRATION for specific dosing recommendations.
Because some strains are resistant to azithromycin, when applicable, appropriate culture and susceptibility tests should be initiated before treatment to determine the causative organism and its susceptibility to azithromycin. Therapy with GD-AZITHROMYCIN may be initiated before results of these tests are known; once the results become available, antibiotic treatment should be adjusted accordingly.
Adults
Pharyngitis and tonsillitis:
Pharyngitis and tonsillitis caused by Streptococcus pyogenes (group A β-hemolytic streptococci) occurring in individuals who cannot use first line therapy.
NOTE: Penicillin is the usual drug of choice in the treatment of Streptococcus pyogenes pharyngitis, including the prophylaxis of rheumatic fever. GD-AZITHROMYCIN is often effective in the eradication of susceptible strains of streptococci from the oropharynx. However, data establishing the efficacy of azithromycin in the subsequent prevention of rheumatic fever are not available at present.
Acute bacterial exacerbations of chronic obstructive pulmonary disease:
Acute bacterial exacerbations of chronic obstructive pulmonary diseases caused by Haemophilus influenzae, Moraxella catarrhalis, or Streptococcus pneumoniae.
Community-acquired pneumonia:
Community-acquired pneumonia caused by Streptococcus pneumoniae, Haemophilus influenzae, Mycoplasma pneumoniae or Chlamydia pneumoniae in patients for whom oral therapy is appropriate.
Azithromycin should not be used in patients with pneumonia who are judged to be inappropriate for oral therapy because of moderate to severe illness or risk factors such as any of the following: patients with cystic fibrosis, patients with nosocomially acquired infections, patients with known or suspected bacteremia, patients requiring hospitalization, elderly or debilitated patients, or patients with significant underlying health problems that may compromise their ability to respond to their illness (including immunodeficiency or functional asplenia).
Uncomplicated skin and skin structure infections:
Uncomplicated skin and skin structure infections caused by Staphylococcus aureus, Streptococcus pyogenes or Streptococcus agalactiae.
Genitourinary tract infections:
Urethritis and cervicitis due to Neisseria gonorrhoeae or Chlamydia trachomatis. Genital ulcer disease in men due to Haemophilus ducreyi (chancroid). Due to the small number of women included in clinical trials, the efficacy of azithromycin in the treatment of chancroid in women has not been established.
Patients should have a serologic test for syphilis and appropriate cultures for gonorrhea performed at the time of diagnosis. Appropriate antimicrobial therapy and follow-up tests for these diseases should be initiated if infection is confirmed.
Pediatrics
Acute otitis media:
Acute otitis media caused by Haemophilus influenzae (β-lactamase positive and negative strains), Moraxella catarrhalis or Streptococcus pneumoniae.
Pharyngitis and tonsillitis:
Pharyngitis and tonsillitis caused by Streptococcus pyogenes (group A β-hemolytic streptococci) occurring in individuals who cannot use first line therapy.
NOTE: Penicillin is the usual drug of choice in the treatment of Streptococcus pyogenes pharyngitis, including the prophylaxis of rheumatic fever. GD-AZITHROMYCIN is often effective in the eradication of susceptible strains of streptococci from the oropharynx. However, data establishing the efficacy of azithromycin in the subsequent prevention of rheumatic fever are not available at present.
Community-acquired pneumonia:
Community-acquired pneumonia caused by Haemophilus influenzae, Streptococcus pneumoniae, Mycoplasma pneumoniae or Chlamydia pneumoniae in patients for whom oral therapy is appropriate.
Azithromycin should not be used in patients with pneumonia who are judged to be inappropriate for outpatient oral therapy because of moderate to severe illness or risk factors such as any of the following: patients with cystic fibrosis, patients with nosocomially acquired infections, patients with known or suspected bacteremia, patients requiring hospitalization, or patients with significant underlying health problems that may compromise their ability to respond to their illness (including immunodeficiency or functional asplenia).
Safety and effectiveness for pneumonia due to Haemophilus influenzae and Streptococcus pneumoniae were not documented bacteriologically in the pediatric clinical trial due to difficulty in obtaining specimens. Use of azithromycin for these two microorganisms is supported, however, by evidence from adequate and well-controlled studies in adults.
Because some strains are resistant to azithromycin, appropriate culture and susceptibility tests should be initiated before treatment to determine the causative organism and its susceptibility to azithromycin. Therapy with GD-AZITHROMYCIN may be initiated before results of these tests are known; once the results become available, antibiotic treatment should be adjusted accordingly.
To reduce the development of drug-resistant bacteria and maintain the effectiveness of GD-AZITHROMYCIN and other antibacterial drugs, GD-AZITHROMYCIN should be used only to treat infections that are proven or strongly suspected to be caused by susceptible bacteria. When culture and susceptibility information are available, they should be considered in selecting or modifying antibacterial therapy. In the absence of such data, local epidemiology and susceptibility patterns may contribute to the empiric selection of therapy.
CONTRAINDICATIONS
GD-AZITHROMYCIN (azithromycin dihydrate) is contraindicated in patients with a history of cholestatic jaundice/hepatic dysfunction associated with prior use of azithromycin and in those with a hypersensitivity to azithromycin, erythromycin, any macrolide or ketolide antibacterial agent, or to any ingredient in the formulation or component of the container. For a complete listing, see DOSAGE FORMS, COMPOSITION AND PACKAGING.
WARNINGS AND PRECAUTIONS
General
Serious allergic reactions, including angioedema, anaphylaxis, and dermatological reactions including Acute Generalized Exanthematous Pustulosis (AGEP), Stevens-Johnson syndrome (SJS), toxic epidermolysis, toxic epidermal necrolysis (TEN) and Drug Reaction with Eosinophilia and Systemic symptoms (DRESS) have been reported rarely (with rare reports of fatalities), in patients on GD-AZITHROMYCIN (azithromycin dihydrate) therapy (see CONTRAINDICATIONS). Allergic reactions may occur during and soon after treatment with GD-AZITHROMYCIN. Despite initially successful symptomatic treatment of the allergic symptoms, when symptomatic therapy was discontinued, the allergic symptoms recurred soon thereafter in some patients without further azithromycin exposure. These patients required prolonged periods of observation and symptomatic treatment. If an allergic reaction occurs, the drug should be discontinued and appropriate therapy should be instituted. Physicians should be aware that reappearance of the allergic symptoms may occur when symptomatic therapy is discontinued.
The use of azithromycin with other drugs may lead to drug-drug interactions. For established or potential drug interactions, see DRUG INTERACTIONS section of the product monograph.
In the absence of data on the metabolism and pharmacokinetics in patients with lysosomal lipid storage diseases (e.g., Tay-Sachs disease, Niemann-Pick disease) the use of GD-AZITHROMYCIN in these patients is not recommended.
Azithromycin and ergot derivatives should not be co-administered due to the possibility that ergot toxicity may be precipitated by macrolide antibiotics. Acute ergot toxicity is characterized by severe peripheral vasospasm, including ischemia of the extremities, along with dysesthesia and possible central nervous system effects.
As with any antibacterial preparation, observation for signs of superinfection with nonsusceptible organisms, including fungi is recommended.
Caution in diabetic patients: 5 ml of reconstituted oral suspension contains 3.87 g of sucrose.
Due to the sucrose content (3.87 g / 5 ml of reconstituted oral suspension), the oral suspension formulation is not indicated for persons with fructose intolerance (hereditary fructose intolerance), glucose-galactose malabsorption or saccharase-isomaltase deficiency.
Due to the lactose content in the tablet coating, patients with rare hereditary problems of galactose intolerance, the Lapp lactase deficiency or glucose-galactose malabsorption should not take the tablet formulation.
Carcinogenesis and Mutagenesis
Long term studies in animals have not been performed to evaluate carcinogenic potential. Azithromycin has shown no genotoxic or mutagenic potential in standard laboratory tests (see TOXICOLOGY).
Cardiovascular
Prolonged cardiac repolarisation and QT interval, imparting a risk of developing cardiac arrhythmia and torsade de pointes, have been seen in treatment with macrolides including azithromycin (see ADVERSE REACTIONS). Prescribers should consider the risk of QT prolongation which can lead to fatal events when weighing the risks and benefits of azithromycin. Risk factors for torsade de pointes include patients:
- With a history of torsade de pointes
- With congenital or documented QT prolongation
- Currently receiving treatment with other active substances known to prolong QT interval such as antiarrhythmics of classes IA and III; antipsychotic agents; antidepressants; and fluoroquinolones.
- With electrolyte disturbance, particularly in cases of hypokalaemia and hypomagnesemia
- With clinically relevant bradycardia, cardiac arrhythmia or cardiac insufficiency
- Elderly may be more susceptible to drug-associated effects on the QT interval
- Exposed to higher plasma levels of azithromycin (e.g. receiving intravenous azithromycin, hepatobiliary impaired)
There is information that 'QT Related Adverse Events' may occur in some patients receiving azithromycin. There have been spontaneous reports from post-marketing experience of prolonged QT interval and torsade de pointes (see ADVERSE REACTIONS, Post marketing Experience). These include but are not limited to: one AIDS patient dosed at 750 mg to 1 g daily experienced prolonged QT interval and torsade de pointes; a patient with previous history of arrhythmias who experienced torsade de pointes and subsequent myocardial infarction following a course of azithromycin therapy; and a pediatric case report of prolonged QT interval experienced at a therapeutic dose of azithromycin which reversed to normal upon discontinuation (see ACTION AND CLINICAL PHARMACOLOGY, Cardiac Electrophysiology).
Gastrointestinal
A higher incidence of gastrointestinal adverse events (8 of 19 subjects) was observed when Azithromycin was administered to a limited number of subjects with GFR<10 mL/min.
Clostridium difficile-associated disease
Clostridium difficile-associated disease (CDAD) has been reported with use of many antibacterial agents including azithromycin. CDAD may range in severity from mild diarrhea to fatal colitis. It is important to consider this diagnosis in patients who present with diarrhea, or symptoms of colitis, pseudomembranous colitis, toxic megacolon, or performation of colon subsequent to the administration of any antibacterial agents. CDAD has been reported to occur over 2 months after the administration of antibacterial agents.
Treatment with antibacterial agents may alter the normal flora of the colon and may permit overgrowth of Clostridium difficile. Clostridium difficile produces toxins A and B which contribute to the development of CDAD. CDAD may cause significant morbidity and mortality. CDAD can be refractory to antimicrobial therapy.
If the diagnosis of CDAD is suspected or confirmed, appropriate therapeutic measures should be initiated. Mild cases of CDAD usually respond to discontinuation of antibacterial agents not directed against Clostridium difficile. In moderate to severe cases, consideration should be given to management with fluids and electrolytes, protein supplementation, and treatment with an antibacterial agent clinically effective against Clostridium difficile. Surgical evaluation should be instituted as clinically indicated, as surgical intervention may be required in certain severe cases (see ADVERSE REACTIONS).
Hematologic
Severe neutropenia (WBC < 1000/mm3) may adversely affect the distribution of azithromycin and its transport to the site of infection. Antibacterials with proven efficacy in this population should be used, as outlined by the relevant guidelines for treatment of patients with severe neutropenia. Efficacy and safety of azithromycin have not been studied in patients with severe neutropenia.
Hepatic/Biliary/Pancreatic
Since the liver is the principal route of elimination for azithromycin, the use of oral GD-AZITHROMYCIN preparations should be undertaken with caution in patients with impaired hepatic function. Azithromycin has not been studied in patients with severe hepatic impairment (see ACTION AND CLINICAL PHARMACOLOGY).
Hepatotoxicity
Abnormal liver function, hepatitis, cholestatic jaundice, hepatic necrosis, and hepatic failure have been reported, some of which have resulted in death. Rare cases of acute hepatic necrosis requiring liver transplant or causing death have been reported in patients following treatment with oral azithromycin. Discontinue azithromycin immediately if signs and symptoms of hepatitis occur (see ADVERSE REACTIONS).
Musculoskeletal and connective tissue disorders
Myasthenia gravis
Exacerbations of symptoms of myasthenia gravis and new onset of myasthenic syndrome have been reported in patients receiving azithromycin therapy. The use of azithromycin in patients with a known history of myasthenia gravis is not recommended.
Renal
The safety, efficacy and pharmacokinetics of azithromycin in patients with renal impairment have not been established. No dose adjustment is recommended for patients with GFR 10-80 mL/min. Caution should be exercised when GD-AZITHROMYCIN is administered to patients with GFR <10 mL/min. This precaution is based on a clinical study of azithromycin immediate-release tablets, in which patients with GFR <10 mL/min showed a significant (61%) increase in mean Cmax and a significant (35%) increase in systemic exposure to azithromycin, and experienced a high incidence of gastrointestinal adverse events (8 of 19 clinical study subjects). Patients with GFR 10-80 mL/min showed only slightly increased serum azithromycin levels compared to patients with normal renal function.
Due to limited data in subjects with GFR <10 mL/min, caution should be exercised when prescribing oral azithromycin in these patients (see ACTIONS AND CLINICAL PHARMACOLOGY).
Sexual Function/Reproduction
There are no adequate and well-controlled studies in humans. In fertility studies conducted in the rat, reduced pregnancy rates were noted following administration of azithromycin. The predictive value of these data to the response in humans has not been established (see TOXICOLOGY).
Susceptibility/Resistance
Development of drug resistant bacteria
Prescribing GD-AZITHROMYCIN in the absence of a proven or strongly suspected bacterial infection is unlikely to provide benefit to the patient and increases the risk of the development of drug-resistant bacteria.
Special Populations
Pregnant Women:
There are no adequate and well-controlled studies in pregnant women. GD-AZITHROMYCIN should not be used during pregnancy unless the expected benefit to the mother outweighs any potential risk to the fetus. In animal reproduction studies in mice and rats, at azithromycin doses up to 200 mg/kg/day (moderately maternally toxic), effects were noted in the rat at 200 mg/kg/day, during the prenatal development period (delayed ossification) and during the postnatal development period (decreased viability, delayed developmental landmarks, differences in performance of learning task). The 200 mg/kg/day dose in mice and rats, is approximately 0.5-fold and 1-fold, respectively, the single adult oral dose of 2 g, based on mg/m2 (body surface area). Pharmacokinetic data from the 200 mg/kg/day dose level in these studies showed that azithromycin crossed the placenta and distributed to fetal tissue at 5 to 9-fold the maternal plasma Cmax of 2 ug/mL (see TOXICOLOGY).
Nursing Women:
Limited information available from published literature indicates that azithromycin is present in human milk at an estimated highest median daily dose of 0.1 to 0.7 mg/kg/day. No serious adverse effects of azithromycin on the breast-fed infants were observed. However, the safety of azithromycin has not been studied in infants less than 6 months of age. Therefore, GD-AZITHROMYCIN should not be used in the treatment of nursing women unless the expected benefit to the mother outweighs any potential risk to the infant. A decision must be made whether to discontinue breast-feeding or to discontinue/abstain from azithromycin therapy taking into account the benefit of breast-feeding for the child and the benefit of therapy for the woman. Because azithromycin may accumulate in breast milk over time with continued GD-AZITHROMYCIN therapy, if the lactating mother is treated with GD-AZITHROMYCIN, the breast milk should be expressed and discarded during treatment.
Pediatrics:
Acute Otitis Media: Safety and efficacy in the treatment of children with otitis media under 6 months of age have not been established.
Community-acquired pneumonia: Safety and efficacy in the treatment of children with community-acquired pneumonia under 6 months of age have not been established.
Pharyngitis and tonsillitis: Safety and efficacy in the treatment of children with pharyngitis and tonsillitis under 2 years of age have not been established.
Studies evaluating the use of repeated courses of therapy have not been conducted. Safety data with the use of azithromycin at doses higher than proposed and for durations longer than recommended are limited to a small number of immunocompromised children who underwent chronic treatment.
Infantile hypertrophic pyloric stenosis (IHPS)
Following the use of azithromycin in neonates (treatment up to 42 days of life), infantile hypertrophic pyloric stenosis (IHPS) has been reported. Parents and caregivers should be informed to contact their physician if vomiting or irritability with feeding occurs.
Geriatrics:
The pharmacokinetics in elderly volunteers (age 65 to 85) were similar to those in younger volunteers (age 18 to 40) for the 5-day oral therapeutic regimen. Dosage adjustment does not appear to be necessary for elderly patients with normal renal and hepatic function receiving treatment with this dosage regimen.
Monitoring and Laboratory Tests
Monitoring of QT/QTc intervals during treatment with GD-AZITHROMYCIN may be considered by the physician as appropriate.
ADVERSE REACTIONS
Adverse Drug Reaction Overview
The majority of side effects observed in controlled clinical trials involving patients (adults and children) treated with oral azithromycin dihydrate were of a mild and transient nature. Approximately 0.7% of both adult patients (n=3812) and children (n=2878) from the 5-day multiple dose clinical trials discontinued azithromycin therapy because of drug related side effects. Among adults receiving azithromycin intravenously, 1.2% of CAP, and 2% of PID patients discontinued treatment. Discontinuation rates were slightly higher for PID patients receiving concomitant metronidazole therapy (4%).
In adults given 500 mg/day for 3 days, the discontinuation rate due to treatment-related side effects was 0.4%. In clinical trials in children given 30 mg/kg, orally either as a single dose (n= 487) or over 3 days, (n=1729) discontinuation from therapy due to treatment-related side effects was approximately 1%.
Most of the side effects leading to discontinuation in patients on oral or intravenous therapy were related to the gastrointestinal tract, e.g., nausea, vomiting, diarrhea, along with abdominal pain, rashes and increases in aminotransferases and/or alkaline phosphatase levels in adult patients receiving intravenous azithromycin. Potentially serious treatment-related side effects including angioedema and cholestatic jaundice occurred in less than 1% of patients.
Clinical Trial Adverse Drug Reactions
Because clinical trials are conducted under very specific conditions the adverse reaction rates observed in the clinical trials may not reflect the rates observed in practice and should not be compared to the rates in the clinical trials of another drug. Adverse drug reaction information from clinical trials is useful for identifying drug-related adverse events and for approximating rates.
Oral Regimen: Adults
Multiple-dose Regimens:
In adult patients, the most common treatment-related side effects in patients receiving the 3 or 5 day oral multiple-dose regimens of GD-AZITHROMYCIN were related to the gastrointestinal system with diarrhea/loose stools (4-5%), abdominal pain (2-3%), vomiting (1%) and nausea (3-4%).
Treatment-related side effects that occurred with a frequency of 1% or less include:
Cardiovascular: hypertension
Gastrointestinal: dry mouth, esophagitis, gastroenteritis, rectal hemorrhage, cholestatic jaundice
Genitourinary: mennorhagia, urinary frequency, vaginitis
Special senses: conjunctivitis
Nervous system: dizziness
Allergic: pruritus
Single 1-gram Dose Regimen:
In adult patients (n=904), side effects that occurred on the single one-gram dosing regimen of azithromycin with a frequency greater than 1% included diarrhea (6.1%), nausea (4.9%), abdominal pain (4.9%), vomiting (1.7%), vaginitis (1.3%), loose stools (1.2%), and dyspepsia (1.1%).
Single 2-gram Dose Regimen:
Overall, the most common side effects in patients receiving a single 2-gram dose of azithromycin were related to the gastrointestinal system. Side effects that occurred in patients in this study with a frequency of a 1% or greater included nausea (18.2%), diarrhea/loose stools (13.8%), vomiting (6.7%), abdominal pain (6.7%), vaginitis (2.2%), dyspepsia (1.1%), and dizziness (1.3%). The majority of these complaints were mild in nature.
Intravenous/Oral Regimen: Adults
The most common side effects (greater than 1%) in adult patients who received sequential I.V./oral azithromycin in studies of community-acquired pneumonia were related to the gastrointestinal system: diarrhea/loose stools (4.3%), nausea (3.9%), abdominal pain (2.7%), and vomiting (1.4%). Approximately 12% of patients experienced a side effect related to the intravenous infusion; most common were pain at the site and/or during the infusion (6.5%) and local inflammation (3.1%).
In adult women who received sequential I.V./oral azithromycin in studies of pelvic inflammatory disease, the most common side effects (greater than 1%) were related to the gastrointestinal system. Diarrhea (8.5%) and nausea (6.6%) were most frequently reported, followed by vaginitis (2.8%), abdominal pain (1.9%), anorexia (1.9%), rash and pruritus (1.9%). When azithromycin was co-administered with metronidazole in these studies, a higher proportion of women experienced side effects of nausea (10.3%), abdominal pain (3.7%), vomiting (2.8%) and application site reaction, stomatitis, dizziness, or dyspnea (all at 1.9%).
Side effects that occurred with a frequency of 1% or less included:
Gastrointestinal: dyspepsia, flatulence, mucositis, oral moniliasis, and gastritis
Nervous System: headache, somnolence
Allergic: bronchospasm
Special Senses: taste perversion
Oral Regimen: Children
Single and Multiple-dose regimens:
In children enrolled in controlled clinical trials in acute otitis media and S. pyogenes pharyngitis, the type of side effects were comparable to those seen in adults (see below).
Different side effect incidence rates for the dosage regimens recommended in children were observed.
Acute Otitis Media: For the recommended total dosage regimen of 30 mg/kg, the most frequent side effects (>1%) attributed to treatment were diarrhea, abdominal pain, vomiting, nausea and rash. The incidence, based on dosing regimen, is described in the table below:
| Regimen | Subjects | Overall ADR Incidence | Diarrhea | Abdominal pain | Vomiting | Nausea | Rash |
| 1-Day | 487 | 14% | 4% | 1% | 5% | 1% | 1% |
| 3-Day | 1395 | 7% | 3% | 2% | 1% | <1% | <1% |
| 5-Day | 1888 | 6% | 2% | 1% | 1% | 1% | <1% |
Community-Acquired Pneumonia: For the recommended total dosage regimen of 30 mg/kg, the most frequent side effects attributed to treatment were diarrhea/loose stools, abdominal pain, vomiting/nausea and rash. The incidence is described in the table below:
| Dosage Regimen | Subjects | Overall ADR Incidence | Diarrhea/ Loose stools | Abdominal Pain | Vomiting | Nausea | Rash |
| 5-day | 323 | 12% | 5.8% | 1.9% | 1.9% | 1.9% | 1.6% |
Pharyngitis/tonsillitis: For the recommended total dosage regimen of 60 mg/kg, the most frequent side effects attributed to treatment were diarrhea, vomiting, abdominal pain, nausea and headache. The incidence is described in the table below:
| Regimen | Subjects | Overall ADR Incidence | Diarrhea | Abdominal pain | Vomiting | Nausea | Rash | Headache |
| 5-Day | 447 | 17% | 5% | 3% | 6% | 2% | <1% | 1% |
Side effects that occurred with a frequency of 1% or less in patients included the following:
| Cardiovascular: | Palpitations, chest pain; |
| Gastrointestinal: | Dyspepsia, flatulence, melena, constipation, anorexia, enteritis, loose stools, oral moniliasis and gastritis; |
| Genitourinary: | Monilia, vaginitis and nephritis; |
| Hematologic and Lymphatic: | Anemia, leukopenia |
| Nervous System: | Dizziness, vertigo, somnolence, agitation, nervousness, insomnia and hyperkinesia; |
| General: | Fatigue, face edema, fever, fungal infection, pain and malaise; |
| Respiratory: | Cough increased, pharyngitis, pleural effusion and rhinitis; |
| Skin and Appendages: | Eczema, fungal dermatitis, sweating and vesiculobullous rash |
| Allergic: | Allergic reaction, photosensitivity, angioedema, erythema multiforme, pruritus and urticaria. |
| Liver/Biliary | Liver function test abnormal, jaundice and cholestatic jaundice. |
Abnormal Hematologic and Clinical Chemistry Findings
Oral Therapy:
Adults:
Clinically significant abnormalities (irrespective of drug relationship) occurring during the clinical trials in patients were reported as follows:
With an incidence of greater than 1%: decreased hemoglobin, hematocrit, lymphocytes, monocytes, albumin and blood glucose, elevated serum creatine phosphokinase, potassium, ALT (SGPT), GGT and AST (SGOT), BUN, creatinine, blood glucose, platelet count, eosinophils and monocytes.
With an incidence of less than 1%: leukopenia, neutropenia, decreased platelet count, elevated serum alkaline phosphatase, bilirubin, LDH and phosphate.
The majority of subjects with elevated serum creatine also had abnormal values at baseline.
When follow-up was provided, changes in laboratory tests appeared to be reversible.
In multiple-dose clinical trials involving more than 4500 patients, 3 patients discontinued therapy because of treatment-related liver enzyme abnormalities, one for treatment-related elevated transaminases and triglycerides and one because of a renal function abnormality.
Children:
One-, Three- and Five-Day Regimens
Laboratory data collected from 64 subjects receiving azithromycin in comparative clinical trials employing the 1-day regimen (30 mg/kg as a single dose), 1198 and 169 subjects receiving azithromycin respectively employing the two 3-day regimens (30 mg/kg or 60 mg/kg in divided doses over 3 days) were similar for regimens of azithromycin and all comparators combined, with most clinically significant laboratory abnormalities occurring at incidences of 1-5%.
Similar results were obtained in subjects receiving the two 5-day regimens. Overall, 1948 and 421 patients were exposed to 30 mg/kg or 60 mg/kg, respectively in divided doses over 5 days. The data collected in the subset of azithromycin patients assessed for laboratory abnormalities were similar to those in all comparators combined with most clinically significant laboratory abnormalities occurring at incidences of 1-5%.
In a single center clinical trial, a decrease in absolute neutrophils was observed in the range of 21-29% for azithromycin regimens of 30 mg/kg given either as a single dose or over 3 days, as well as the comparator. No patients had significant neutropenia defined as an absolute neutrophil count <500 cells/mm3 (see CLINICAL TRIALS).
In clinical trials involving approximately 4700 pediatric patients, no patients discontinued therapy because of treatment-related laboratory abnormalities.
Intravenous Therapy
Adults:
With an incidence of 4-6%, elevated ALT, AST, and creatinine.
With an incidence of 1-3%, elevated LDH and bilirubin.
With an incidence of less than 1%, leukopenia, neutropenia, decreased platelet count, and elevated serum alkaline phosphatase.
In multiple dose clinical trials involving more than 750 patients treated with sequential I.V./oral azithromycin less than 2% of patients discontinued therapy because of treatment-related liver enzyme abnormalities.
When follow-up was provided, changes in laboratory tests appeared to be reversible for both oral and I.V. dosing.
Post-Market Adverse Drug Reactions
The following adverse experiences have been reported in patients under conditions (e.g., open trials, marketing experience) where a causal relationship is uncertain or in patients treated with significantly higher than the recommended doses for prolonged periods.
In addition, because these reactions are reported voluntarily from a population of uncertain size, reliably estimating their frequency is not always possible.
| Allergic: Arthralgia, edema, anaphylaxis (with rare reports of fatalities) (see WARNINGS AND PRECAUTIONS), serum sickness, urticaria, vasculitis, angioedema, pruritus; |
Blood and the lymphatic system Agranulocytosis, haemolytic anaemia, thrombocytopenia disorders: |
| Cardiovascular: Cardiac arrhythmias (including ventricular tachycardia), palpitations, hypotension. There have been rare reports of QT prolongation and torsade de pointes in patients receiving therapeutic doses of azithromycin, including a pediatric case report of QT interval prolongation which reversed to normal upon discontinuation (see WARNINGS AND PRECAUTIONS). |
| Gastrointestinal: Anorexia, constipation, hypoglycaemia, dehydration, vomiting/diarrhea rarely resulting in dehydration, pancreatitis, pseudomembranous colitis, rare reports of tongue discoloration, pyloric stenosis / infantile hypertrophic pyloric stenosis (IHPS); |
| General: Asthenia, paresthesia, fatigue, muscle pain; |
| Genitourinary: Interstitial nephritis, acute renal failure, nephrotic syndrome, vaginitis; |
| Liver/Biliary: Hepatitis fulminant. Abnormal liver function including drug-induced hepatitis and cholestatic jaundice have been reported. There have also been rare cases of hepatic necrosis and hepatic failure, which have resulted in death (see WARNINGS AND PRECAUTIONS). |
Musculoskeletal and connective myasthenia gravis tissue disorders: |
| Nervous System: Dizziness, hyperactivity, hypoaesthesia, seizure, convulsions, and syncope |
Psychiatric Aggressive reaction, anxiety, nervousness, agitation, delirium, hallucinations Disorders: Skin/Appendages: Serious skin reactions including erythema multiforme, exfoliative dermatitis, Acute Generalized Exanthematous Pustulosis (AGEP), Stevens-Johnson syndrome (SJS), toxic epidermal necrolysis (TEN), drug reaction with eosinophilia and systemic symptoms (DRESS) (see WARNINGS and PRECAUTIONS). |
| Special Senses: Hearing disturbances including hearing loss, hearing impaired, deafness and / or tinnitus, vertigo, taste/smell perversion and/or loss, abnormal vision. |
DRUG INTERACTIONS
Overview
Caution is warranted when azithromycin is administered to a patient with a history of a significant cardiac repolarization disorder or who is taking other medicinal products that cause a prolonged QT interval (see WARNINGS AND PRECAUTIONS, Cardiovascular and
ADVERSE REACTIONS, Post-Marketing Experience).
Azithromycin does not interact significantly with the hepatic cytochrome P450 system. It is not believed to undergo the cytochrome P450-related drug interactions seen with erythromycin and other macrolides. Hepatic cytochrome P450 induction or inhibition via cytochrome metabolite complex does not occur with azithromycin.
Concomitant administration of azithromycin with P-glycoprotein substrates may result in increased serum levels of P-glycoprotein substrates. Concomitant administration of P-glycoprotein inhibitors with azithromycin sustained-release form had minimal effect on the pharmacokinetics of azithromycin.
Drug-Drug Interactions
Established or Potential Drug-Drug Interactions
| Proper name | Ref | Effect | Clinical comment |
Antacids Aluminum and magnesium containing antacids (Maalox®) | CT | Reduce the peak serum levels but not the extent of azithromycin absorption | GD-AZITHROMYCIN and these drugs should not be taken simultaneously |
| Carbamazepine | CT | In a Pharmacokinetic interaction study in healthy volunteers no significant effect was observed on the plasma levels of carbamazepine or its active metabolite in patients receiving concomitant azithromycin. | |
| Cetirizine | CT | In healthy male volunteers, co-administration of a 5-day regimen of azithromycin with cetirizine 20 mg at steady-state resulted in no pharmacokinetic interaction and no significant changes in the QT interval. | |
| Cimetidine | CT | Administration of a single-dose of cimetidine (800 mg) two hours prior to azithromycin had no effect on azithromycin absorption or on azithromycin pharmacokinetics. | |
| Coumarin-Type Oral Anticoagulants | CT | In a pharmacokinetic interaction study of 22 healthy men, a 5-day course of azithromycin did not affect the prothrombin time from a subsequently administered single 15 mg dose of warfarin Spontaneous post-marketing reports suggest that concomitant administration of azithromycin may potentiate the effects of oral anticoagulants | Prothrombin times should be carefully monitored while patients are receiving azithromycin and concomitantly-administered oral anticoagulants. |
| Cyclosporine | CT | In a pharmacokinetic study with healthy volunteers that were administered a 500 mg/day oral dose of azithromycin for 3 days and were then administered a single 10 mg/kg oral dose of cyclosporine, the resulting cyclosporine Cmax and AUC0-5 were found to be significantly elevated | Caution should be exercised before considering concurrent administration of these drugs. If co administration of these drugs is necessary, cyclosporine levels should be monitored and the dose adjusted accordingly. |
| Didanosine | CT | Daily doses of 1200 mg azithromycin had no effect on the pharmacokinetics of didanosine | |
| Efavirenz | CT | Efavirenz, when administered at a dose of 400 mg for seven days produced a 22% increase in the Cmax of azithromycin administered as a 600 mg single dose. AUC was not affected. Administration of a single 600 mg dose of azithromycin immediate-release had no effect on the pharmacokinetics of efavirenz given at 400 mg doses for seven days. | |
| Fluconazole | CT | A single dose of 1200 mg azithromycin immediate-release did not alter the pharmacokinetics of a single 800 mg oral dose of fluconazole. Total exposure and half-life of 1200 mg azithromycin were unchanged and Cmax had a clinically insignificant decrease (18%) by coadministration with 800 mg fluconazole. | |
| HMG-CoA Reductase Inhibitors | CT | In healthy volunteers, co-administration of atorvastatin (10 mg daily) and azithromycin immediate-release (500 mg daily) did not alter plasma concentrations of atorvastatin (based on HMG CoA-reductase inhibition assay). However, post-marketing cases of rhabdomyolysis in patients receiving azithromycin with statins have been reported. | |
| Indinavir | CT | A single dose of 1200 mg azithromycin immediate-release had no significant effect on the pharmacokinetics of indinavir (800 mg indinavir three times daily for 5 days). | |
| Midazolam | CT | In healthy volunteers (N=12), co-administration of azithromycin immediate-release 500 mg/day for 3 days did not cause clinically significant changes in the pharmacokinetics and pharmacodynamics of a single 15 mg dose of midazolam. |
| Nelfinavir | CT | Coadministration of a single dose of 1200 mg azithromycin immediate-release with steady-state nelfinavir (750 mg three times daily) produced an approximately 16% decrease in mean AUC0-8 of nelfinavir and its M8 metabolite. Cmax was not affected. Coadministration of nelfinavir (750 mg three times daily) at steady-state with a single dose of 1200 mg azithromycin immediate-release increased the mean AUC0-∞ of azithromycin by 113% and mean Cmax by 136%. | Dose adjustment of GD-AZITHROMYCIN is not recommended. However, close monitoring for known side effects of azithromycin, when administered in conjunction with nelfinavir, is warranted. |
| P-glycoprotein inhibitors | CT | Co-administration of P-glycoprotein inhibitors (Vitamin E, Poloxamer 407, or Poloxamer 124) with azithromycin sustained release form (1 gram dose) had minimal effect on the pharmacokinetics of azithromycin. | |
| Rifabutin | CT | Co-administration of azithromycin and rifabutin did not affect the serum concentrations of either drug. Neutropenia was observed in subjects receiving concomitant treatment with azithromycin and rifabutin. | Neutropenia has been associated with the use of rifabutin, but it has not been established if concomitantly-administered azithromycin potentiates that effect (see ADVERSE REACTIONS). |
| Sildenafil | CT | In normal healthy male volunteers, there was no evidence of a statistically significant effect of azithromycin immediate-release (500 mg daily for 3 days) on the AUC, Cmax, Tmax, elimination rate constant, or subsequent half-life of sildenafil or its principal circulating metabolite. | |
| Theophylline | CT | Concurrent use of macrolides and theophylline has been associated with increases in the serum concentrations of theophylline. Azithromycin did not affect the pharmacokinetics of theophylline administered either as a single intravenous infusion or multiple oral doses at a recommended dose of 300 mg every 12 hours. There is one post-marketing report of supraventricular tachycardia associated with an elevated theophylline serum level that developed soon after initiation of treatment with azithromycin. | Until further data are available, prudent medical practice dictates careful monitoring of plasma theophylline levels in patients receiving GD-AZITHROMYCIN and theophylline concomitantly. |
| Trimethoprim/ Sulfamethoxazole | CT | Co-administration of trimethoprim/sulfamethoxazole (160 mg/800 mg) for 7 days with azithromycin immediate-release 1200 mg on Day 7 had no significant effect on peak concentrations, total exposure or urinary excretion of either trimethoprim or sulfamethoxazole. Azithromycin serum concentrations were similar to those seen in other studies. |
| Zidovudine | CT | Single 1 g doses and multiple 1200 mg or 600 mg doses of azithromycin did not affect the plasma pharmacokinetics or urinary excretion of zidovudine or its glucuronide metabolite. However, administration of azithromycin increased the concentrations of phosphorylated zidovudine, the clinically active metabolite in peripheral blood mononuclear cells. |
Legend: C = Case Study; CT = Clinical Trial; T = Theoretical; UNK=Unknown
Concomitant Therapy
The following drug interactions have not been reported in clinical trials with azithromycin and no specific drug interaction studies have been performed to evaluate potential drug-drug interactions. Nonetheless, they have been observed with macrolide products, and there have been rare spontaneously reported cases with azithromycin and some of these drugs, in post marketing experience. Until further data are developed regarding drug interactions, when
GD-AZITHROMYCIN and these drugs are used concomitantly, careful monitoring of patients is advised both during and for a short period following therapy:
Antihistamines
Prolongation of QT intervals, palpitations or cardiac arrhythmias have been reported with concomitant administration of azithromycin and astemizole or terfenadine.
Cisapride, Hexobarbital, Phenytoin
Increased serum levels of hexobarbital, cisapride or phenytoin have been reported.
Digoxin and colchicine / P-glycoprotein substrates
Concomitant administration of some macrolide antibiotics with P-glycoprotein substrates, including digoxin and colchicine, has been reported to result in increased serum levels of the P-glycoprotein substrate. Therefore, if azithromycin and P-gp substrates such as digoxin are administered concomitantly, the possibility of elevated serum digoxin concentrations should be considered. Clinical monitoring, and possibly serum digoxin levels, during treatment with azithromycn and after its discontinuation are necessary.
Disopyramide: Azithromycin may increase the pharmacologic effect of disopyramide.
Ergot (ergotamine or dihydroergotamine)
Azithromycin and ergot derivatives should not be co-administered due to the possibility that ergot toxicity may be precipitated by some macrolide antibiotics. Acute ergot toxicity is characterized by severe peripheral vasospasm including ischemia of the extremities, along with dysesthesia and possible central nervous system effects.
Gentamicin
No data are available on the concomitant clinical use of azithromycin and gentamicin or other amphiphilic drugs which have been reported to alter intracellular lipid metabolism.
Triazolam
Azithromycin may decrease the clearance of triazolam and increase the pharmacologic effect of triazolam.
Drug-Food Interactions
Azithromycin tablets and powder for oral suspension can be taken with or without food.
Drug-Herb Interactions
Interactions with herbal products have not been established.
Drug-Laboratory Interactions
Interactions with laboratory tests have not been established.
DOSAGE AND ADMINISTRATION
Dosing Considerations
GD-AZITHROMYCIN immediate-release oral formulations (tablets or oral suspension) are not bioequivalent and are not interchangeable with azithromycin sustained release due to a different pharmacokinetic profile (see DETAILED PHARMACOLOGY).
General
Hepatic Impairment:
No dose adjustment of oral GD-AZITHROMYCIN preparations is recommended for patients with mild to moderate hepatic impairment. Azithromycin has not been studied in patients with severe hepatic impairment. Since the liver is the principal route of elimination for azithromycin, the use of oral GD-AZITHROMYCIN preparations should be undertaken with caution in patients with impaired hepatic function (see WARNINGS AND PRECAUTIONS and ACTION AND CLINICAL PHARMACOLOGY).
Renal Impairment:
No dosage adjustment of oral GD-AZITHROMYCIN preparations is recommended for subjects with mild to moderate (GFR 10-80 mL/min) renal impairment. The mean AUC0-120 increased 35% in subjects with GFR <10 mL/min compared to subjects with normal renal function. Caution should be exercised when azithromycin is administered to subjects with severe renal impairment. No studies have been conducted in patients requiring hemodialysis (see ACTIONS AND CLINICAL PHARMACOLOGY and WARNINGS AND PRECAUTIONS).
Recommended Dose and Dosage Adjustment
GD-AZITHROMYCIN for ORAL THERAPY
ADULTS
DOSING in relation to FOOD:
TABLETS: GD-AZITHROMYCIN Tablets can be taken with or without food.
UPPER AND LOWER RESPIRATORY INFECTIONS/ SKIN AND SKIN STRUCTURE INFECTIONS:
The recommended dose of GD-AZITHROMYCIN for individuals 16 years of age or older in the treatment of mild to moderate acute bacterial exacerbations of chronic obstructive pulmonary disease due to the indicated organisms is: either 500 mg per day for 3 days or 500 mg as a single dose on the first day followed by 250 mg once daily on days 2 through 5 for a total dose of 1.5 grams.
The recommended dose of GD-AZITHROMYCIN for the treatment of community-acquired pneumonia of mild severity, uncomplicated skin and skin structure infections, and for pharyngitis/tonsillitis (as second-line therapy) due to the indicated organisms is: 500 mg as a single dose on the first day followed by 250 mg once daily on days 2 through 5 for a total dose of 1.5 grams.
GENITOURINARY INFECTIONS:
The recommended dose of GD-AZITHROMYCIN for the treatment of genital ulcer disease due to Haemophilus ducreyi (chancroid) and non-gonococcal urethritis and cervicitis due to C. trachomatis is: a single 1 gram (1000 mg) oral dose of GD-AZITHROMYCIN. This dose can be administered as four 250 mg tablets.
The recommended dose of GD-AZITHROMYCIN for the treatment of urethritis and cervicitis due to Neisseria gonorrhoeae is: a single 2 gram (2000 mg) dose of GD-AZITHROMYCIN. This dose can be administered as eight 250 mg tablets.
CHILDREN
DOSING in relation to FOOD:
POWDER FOR ORAL SUSPENSION: GD-AZITHROMYCIN Powder for Oral Suspension can be taken with or without food (see ACTION AND CINICAL PHARMACOLOGY).
PEDIATRIC DOSING GUIDELINES:
The recommended total dose for children is 30 mg/kg for otitis media and community acquired pneumonia. For pharyngitis/tonsillitis, the recommended total dose is 60 mg/kg.
| Indication | 1-Day | 3-Day | 5-Day |
Acute Otitis Media Pharyngitis/ Tonsillitis Community-Acquired Pneumonia | 30 mg/kg | 10 mg/kg/day | Day 1: 10 mg/kg Day 2-5: 5 mg/kg 12 mg/kg/day Day 1: 10 mg/kg Day 2-5: 5 mg/kg |
ACUTE OTITIS MEDIA:
The recommended dose of GD-AZITHROMYCIN oral suspension for the treatment of children with acute otitis media is 30 mg/kg given as a single dose (not to exceed 1500 mg) or 10 mg/kg once daily for 3 days (not to exceed 500 mg/day) or 10 mg/kg as a single dose on the first day (not to exceed 500 mg/day) followed by 5 mg/kg/day on days 2 through 5 (not to exceed 250 mg/day). (See chart #1, 2 and 3 respectively below).
The safety of re-dosing azithromycin in children who vomit after receiving 30 mg/kg as a single dose has not been established. In clinical studies involving 487 patients with acute otitis media given a single 30 mg/kg dose of azithromycin, eight patients who vomited within 30 minutes of dosing were re-dosed at the same total dose.
COMMUNITY-ACQUIRED PNEUMONIA:
The recommended dose of GD-AZITHROMYCIN for oral suspension for the treatment of children with community-acquired pneumonia is 10 mg/kg as a single dose on the first day (not to exceed 500 mg/day) followed by 5 mg/kg on days 2 through 5 (not to exceed 250 mg/day). (See chart #3 below).
Effectiveness of the 3-day or 1-day regimen in children with community-acquired pneumonia has not been established.
PHARYNGITIS AND TONSILLITIS:
The recommended dose for children with pharyngitis and tonsillitis is 12 mg/kg once daily for 5 days (not to exceed 500 mg/day). (See chart #4 below).
PEDIATRIC DOSAGE GUIDELINES
BASED on BODY Weight
CHART #1
OTITIS MEDIA: (1-Day Regimen)* Dosing Calculated on 30 mg/kg as a single dose Age 6 months and above, see WARNINGS and PRECAUTIONS-Pediatric Use | ||||
| Weight | 200 mg/5 mL | Total mL per Treatment Course | Total mg per Treatment Course | |
| Kg | Lbs. | Day 1 | ||
| 5 | 11 | 3.75 mL (3/4 tsp) | 3.75 mL | 150 mg |
| 10 | 22 | 7.5 mL (1 ½ tsp) | 7.5 mL | 300 mg |
| 20 | 44 | 15 mL (3 tsp) | 15 mL | 600 mg |
| 30 | 66 | 22.5 mL (4 ½ tsp) | 22.5 mL | 900 mg |
| 40 | 88 | 30 mL (6 tsp) | 30 mL | 1200 mg |
| 50 and above | 110 and above | 37.5 mL (7 ½ tsp) | 37.5 mL | 1500 mg |
* Effectiveness of the 1-day regimen in children with community-acquired pneumonia has not been established.
CHART #2
OTITIS MEDIA: (3-Day Regimen)* Dosing Calculated on 10 mg/kg/day Age 6 months and above, see WARNINGS and PRECAUTIONS-Pediatric Use | |||||
| Weight | 100 mg/5 mL | 200 mg/5 mL | Total mL per Treatment Course | Total mg per Treatment Course | |
| Kg | Lbs. | Day 1-3 | Day 1-3 | ||
| 5 | 11 | 2.5 mL (1/2 tsp) | 7.5 mL | 150 mg | |
| 10 | 22 | 5 mL (1 tsp) | 15 mL | 300 mg | |
| 20 | 44 | 5 mL (1 tsp) | 15 mL | 600 mg | |
| 30 | 66 | 7.5 mL (1 ½ tsp) | 22.5 mL | 900 mg | |
| 40 | 88 | 10 mL (2 tsp) | 30 mL | 1200 mg | |
| 50 and above | 110 and above | 12.5 mL (2 ½ tsp) | 37.5 mL | 1500 mg | |
*Effectiveness of the 3-day regimen in children with community-acquired pneumonia has not been established.
CHART #3
ACUTE OTITIS MEDIA OR COMMUNITY-ACQUIRED PNEUMONIA Age 6 months and above, see WARNINGS and PRECAUTIONS-Pediatric Use 5-Day Regimen | |||||||
| Dosing Calculated on 10 mg/kg on Day 1 dose, followed by 5 mg/kg on Days 2 to 5 | |||||||
| Weight | 100 mg/5 mL Suspension | 200 mg/5 mL Suspension | Total mL per Treatment Course | Total mg per Treatment Course | |||
| Kg | lbs | Day 1 | Days 2-5 | Day 1 | Days 2-5 | ||
| 5 | 11 | 2.5 mL (½ tsp) | 1.25 mL (¼ tsp) | 7.5 mL | 150 mg | ||
| 10 | 22 | 5 mL (1tsp) | 2.5 mL (½ tsp) | 15 mL | 300 mg | ||
| 20 | 44 | 5 mL (1 tsp) | 2.5 mL (½ tsp) | 15 mL | 600 mg | ||
| 30 | 66 | 7.5 mL (1½ tsp) | 3.75 mL (¾ tsp) | 22.5 mL | 900 mg | ||
| 40 | 88 | 10 mL (2tsp) | 5 mL (1tsp) | 30 mL | 1200 mg | ||
| 50 and above | 110 and above | 12.5mL (2½ tsp) | 6.25 mL (1¼ tsp) | 37.5 mL | 1500 mg | ||
CHART # 4
PHARYNGITIS AND TONSILLITIS: (5-Day Regimen) (Age 2 years and above see WARNINGS and PRECAUTIONS-Pediatric Use) | ||||
| Dosing Calculated on 12 mg/kg once daily Days 1 to 5 | ||||
| Weight | 200 mg/5 mL Suspension | Total mL per Treatment Course | Total mg per Treatment Course | |
| Kg | Lbs | Day 1-5 | ||
8 17 25 33 40 | 18 37 55 73 88 | 2.5 mL (½ tsp) 5 mL (1tsp) 7.5 mL (1½ tsp) 10 mL (2 tsp) 12.5 mL (2 ½ tsp) | 12.5 mL 25 mL 37.5 mL 50 mL 62.5 mL | 500 mg 1000 mg 1500 mg 2000 mg 2500 mg |
Administration
Reconstitution:
GD-AZITHROMYCIN Powder for Oral Suspension:
Tap bottle to loosen powder. Add the directed volume of water. Shake well before each use.
Oversized bottle provides shake space. Keep tightly closed. The table below indicates the volume of water to be used for reconstitution:
Amount of water to be added | Nominal volume after reconstitution (azithromycin content) | Azithromycin concentration after reconstitution |
9 mL (300 mg bottle) 9 mL (600 mg bottle) 12 mL (900 mg bottle) | 15 mL (300 mg bottle) 15 mL (600 mg bottle) 22.5 mL (900 mg bottle) | 100 mg/5 mL 200 mg/5 mL 200 mg/5 mL |
Use only the dosing device provided to measure the correct amount of suspension (see DOSAGE FORMS, COMPOSITION AND PACKAGING). The dosing device may need to be filled multiple times to provide the complete dose prescribed. Rinse the device with water after the complete daily dose has been administered.
Following constitution, and for use with the oral syringe, the supplied plastic stopper should be inserted into the neck of the bottle then sealed with the original closure.
OVERDOSAGE
Activated charcoal may be administered to aid in the removal of unabsorbed drug. General supportive measures are recommended.
Ototoxicity and gastrointestinal adverse events may occur with an overdose of azithromycin.
Up to 15 grams cumulative dose of azithromycin dihydrate over 10 days has been administered in clinical trials without apparent adverse effect.
Adverse events experienced in higher than recommended doses were similar to those seen at normal doses.
| For management of a suspected drug overdose, contact your regional Poison Control Centre. |
ACTION AND CLINICAL PHARMACOLOGY
Mechanism of Action
GD-AZITHROMYCIN (azithromycin dihydrate), a macrolide antibiotic of the azalide subclass, exerts its antibacterial action by binding to the 23S rRNA of the 50s ribosomal subunits of susceptible bacteria. It blocks protein synthesis by inhibiting the transpeptidation/translocation step of protein synthesis and by inhibiting the assembly of the 50S ribosomal subunit.
Pharmacodynamics
Cardiac Electrophysiology:
QTc interval prolongation was studied in a randomized, placebo-controlled parallel trial. A total of 119 healthy subjects were enrolled (mean age of 35.5 years; range 18-55 years), of which 116 subjects (97 males) completed the study and were included in the analysis. Subjects were randomized to one of 5 treatments and received orally once daily for 3 days: placebo, chloroquine 600 mg base only, or chloroquine 600 mg base in combination with azithromycin 500 mg, 1000 mg, and 1500 mg. On Day 3, the azithromycin mean (%CV) plasma Cmax values for the 500, 1000 and 1500 mg azithromycin dose regimens were 0.536 (33), 0.957 (31), and 1.54 (28) µg/mL, respectively. Co-administration of azithromycin increased the QTc interval in a dose- and concentration-dependent manner. In comparison to chloroquine alone, the day 3 maximum mean (90% upper confidence bound) increases in QTcF were 5 (10) ms, 7 (12) ms and 9 (14) ms with the co-administration of 500 mg, 1000 mg and 1500 mg azithromycin, respectively.
Pharmacokinetics
No data exist in humans in regard to the extent of accumulation, duration of exposure, metabolism or excretory mechanisms of azithromycin in neural tissue such as the retina and the cochlea.
Adult Pharmacokinetics:
Plasma concentrations of azithromycin decline in a polyphasic pattern, resulting in an average terminal half-life of 68 hours. The prolonged half-life is likely due to extensive uptake and subsequent release of drug from tissues. Over the dose range of 250 to 1000 mg orally, the serum concentrations are related to dose.
In adults, the following pharmacokinetic data have been reported:
| DOSE/DOSAGE FORM | Subjects | Cmax (µg/mL) | Tmax (hr) | AUC (µ•hr/mL) | T½ (hr) |
500 mg/250 mg tablet 500 mg/250 mg tablet | 12; fasted 12; fed | 0.34 0.41 | 2.1 2.3 | 2.49a 2.40a | - - |
a 0-48 hr
Absorption:
Following oral administration, azithromycin is rapidly absorbed (Tmax = 2-3 hours) and distributed widely throughout the body, (see DETAILED PHARMACOLOGY).
The absolute bioavailability is approximately 37%.
When azithromycin suspension was administered with food to 28 adult healthy male subjects, the rate of absorption (Cmax) was increased by 56% while the extent of absorption (AUC) was unchanged. Food does not affect the absorption of azithromycin in the tablet dosage form. Azithromycin tablets and powder for oral suspension can be taken with or without food.
Distribution:
The serum protein binding of azithromycin is concentration dependent, decreasing from 51% at 0.02 μg/mL to 7% at 2.0 μg/mL. Following oral administration, azithromycin is widely distributed throughout the body with a steady-state apparent volume of distribution of 31.1 L/kg.
Rapid movement of azithromycin from blood into tissue results in significantly higher azithromycin concentrations in tissue than in plasma (up to 50 times the maximum observed concentration in plasma), (see DETAILED PHARMACOLOGY).
The long tissue half-life and large volume of distribution result from intracytoplasmic uptake and storage in lysosomal phospholipid complexes.
Metabolism:
The majority of systemically available azithromycin is excreted unchanged in the bile. Metabolites of azithromycin were identified in bile but have not been studied further, (see DETAILED PHARMACOLOGY).
Excretion:
Biliary excretion of azithromycin, predominantly as unchanged drug, is a main route of elimination. Over the course of a week, approximately 6% of the administered dose appears as unchanged drug in the urine, (see DETAILED PHARMACOLOGY).
Special Populations and Conditions
Pediatric Pharmacokinetics:
Pharmacokinetics in children receiving a total dose of 30 mg/kg:
The table below shows mean pharmacokinetic parameters on day 5 in children 1 to 5 years and 5 to 15 years of age when azithromycin oral suspension was dosed in the absence of food at a total dose of 30 mg/kg delivered as 10 mg/kg on day 1 and 5 mg/kg on days 2-5.
Pharmacokinetics in children given a total dose of 30 mg/kg delivered as a single dose have not been studied.
| Pharmacokinetic parameters on day 5 at dosage 10 mg/kg (day 1) and 5 mg/kg (days 2-5) | |||||||||||
| Age 1-5 | Age 5-15 | ||||||||||
Cmax (µg/mL) | Tmax (hrs) | AUC0-24 (µg•hr/mL) | Cmax (µg/mL) | Tmax (hrs) | AUC0-24 (µg•hr/mL) | ||||||
| 0.216 | 1.9 | 1.822 | 0.383 | 2.4 | 3.109 | ||||||
Pharmacokinetics in children receiving a 60 mg/kg total dose:
Two clinical studies enrolled 35 and 33 children respectively aged 3-16 years with pharyngitis/tonsillitis to determine the pharmacokinetics and safety of azithromycin for oral suspension in children when given 60 mg/kg in divided doses delivered as 20 mg/kg/day over 3 days or 12mg/kg/day over 5 days with a maximum daily dose of 500 mg.
The following table shows pharmacokinetic data in the subset of children who received a total dose of 60 mg/kg. In both studies azithromycin concentrations were determined over a 24 hour period following the last daily dose.
Similarity of overall exposure (AUC 0-∞) between the 3 and 5 day regimen is unknown.
3-Day Regimen (20mg/kg x 3 days) | 5-Day Regimen (12 mg/kg x 5 days) | ||||||||
| N | 11B | 17B | |||||||
| Cmax (μg/mL) | 1.05 ± .44a | 0.534 ± 0.361a | |||||||
| Tmax (hr) | 3 ± 2.0a | 2.2 ± 0.8a | |||||||
| AUC0-24(μg ×hr/mL) | 7.92 ± 2.87a | 3.94 ± 1.90a | |||||||
a Arithmetic means B maximum weight for 3 day regimen was < 25 kg and for 5 day regimen was <41.7 kg | |||||||||
Geriatrics:
When studied in healthy elderly subjects from age 65 to 85 years, the pharmacokinetic parameters of azithromycin in elderly men were similar to those in young adults; however, in elderly women, although higher peak concentrations (increased by 30 to 50%) were observed, no significant accumulation occurred.
Gender:
There are no significant differences in the disposition of immediate-release azithromycin between male and female subjects. No dosage adjustment is recommended based on gender.
Hepatic Insufficiency:
In patients with mild to moderate hepatic impairment, there is no evidence of a marked change in serum pharmacokinetics of oral GD-AZITHROMYCIN compared to those with normal hepatic function. In these patients urinary recovery of azithromycin appears to increase. Hence no dose adjustment is recommended for patients with mild to moderate hepatic impairment. Azithromycin has not been studied in patients with severe hepatic impairment.
Renal Insufficiency:
Azithromycin pharmacokinetics were investigated in 42 adults (21 to 85 years of age) with varying degrees of renal impairment. Following the oral administration of a single 1,000 mg dose of azithromycin, mean Cmax and AUC0-120 increased by 5.1% and 4.2%, respectively in subjects with mild to moderate renal impairment (GFR 10 to 80 mL/min) compared to subjects with normal renal function (GFR >80 mL/min). The mean Cmax and AUC0-120 increased 61% and 35%, respectively in subjects with severe renal impairment (GFR <10 mL/min) compared to subjects with normal renal function (GFR >80 mL/min).
STORAGE AND STABILITY
Store GD-AZITHROMYCIN Film-Coated Tablets at controlled room temperature (15-30°C).
Powder for Oral Suspension:
Dry powder: Store at controlled room temperature (15-30°C).
Reconstituted suspension: Store between 5°C and 30°C. Discard unused portion after 10 days.
DOSAGE FORMS, COMPOSITION AND PACKAGING
TABLETS 250 mg: Each pink, film-coated, modified capsular-shaped GD-AZITHROMYCIN tablet, engraved “Pfizer” on the upper face, “306” or scored on the lower face, contains azithromycin dihydrate equivalent to 250 mg of azithromycin and the following inactive ingredients: pregelatinized starch (27 mg), anhydrous calcium phosphate dibasic, sodium croscarmellose (9 mg), magnesium stearate, sodium lauryl sulphate, hydroxypropyl methylcellulose, lactose (tablet coating), titanium dioxide, triacetin and D&C Red #30 aluminum lake. The tablets are packaged in white plastic (high density polyethylene) bottles of 30 and 100 or in a single treatment package (Z-pak) of 6 blister packaged tablets per box.
POWDER FOR ORAL SUSPENSION: GD-AZITHROMYCIN Powder for Oral Suspension, contains azithromycin dihydrate equivalent to: 300 mg; 600 mg; and 900 mg of azithromycin per bottle. After reconstitution, each bottle (high density polyethylene) contains a cherry flavoured suspension with azithromycin dihydrate equivalent to: 300 mg per 15 mL (100 mg/5 mL); 600 mg per 15 mL (200 mg/5 mL); 900 mg per 22.5 mL (200 mg/5 mL) azithromycin. The non-medicinal ingredients include: sucrose (3.86 g per 100 mg/5 mL and 3.87 g per 200 mg/5 mL); sodium phosphate (8.76 mg per 100 mg/5 mL and 17.50 per 200 mg/5 mL), tribasic hydroxypropyl cellulose; xanthan gum; FD&C Red #40 and artificial flavours (see DOSAGE AND ADMINISTRATION, Reconstitution Directions). The 300 mg bottle (100 mg/5 mL) is supplied with a plastic stopper and a calibrated syringe. The 600 mg bottle (200 mg/5 mL) and the 900 mg bottle (200 mg/5 mL) are supplied with a plastic stopper, and a calibrated syringe and dosing cup.
PART II: SCIENTIFIC INFORMATION
PHARMACEUTICAL INFORMATION
Drug Substance
Proper name: azithromycin dihydrate
Chemical name: 9-deoxo-9α-aza-9α-methyl-9α-homoerythromycin A dihydrate.
Molecular formula and molecular mass: C38H76N2014 and 785.0
Structural formula:
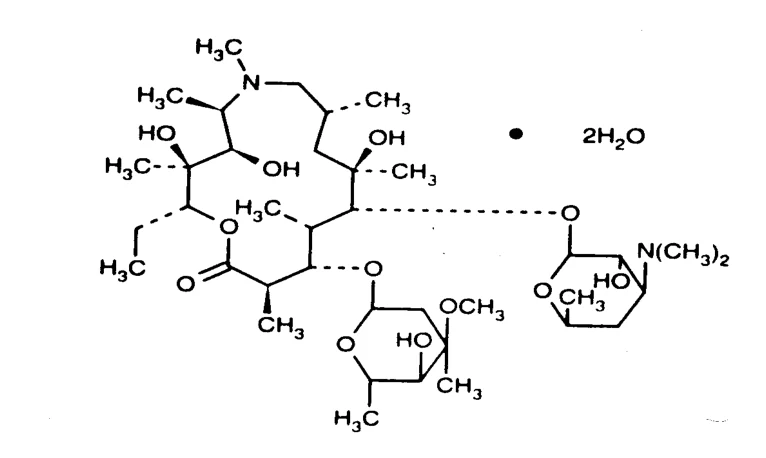
Physicochemical properties: Azithromycin dihydrate is a white to off-white crystalline powder of uniform appearance. The aqueous solubility at pH 7.4 at 37°C is 39 mg/mL. The powder is non-hygroscopic.
pKa: 8.48
Melting point: 125°C
CLINICAL TRIALS
From the perspective of evaluating clinical trials because of the extended half-life of azithromycin, days 11-14 (10-13 days after completion of the one-day regimen, 8-11 days after completion of the three-day regimen or 6-9 days after completion of the five-day regimen) were considered on-therapy evaluations and are provided for clinical guidance. Day 21-30 evaluations were considered the primary test of cure endpoint. For patients with community-acquired pneumonia, Days 15-19 were considered as on-therapy evaluations. Days 28-42 were the cure endpoint.
Pediatric Patients:
Otitis Media:
Efficacy using azithromycin 30 mg/kg given over 5 days
Protocol 1
In a double-blind, controlled clinical study of acute otitis media performed in North America, azithromycin (10 mg/kg on day 1 followed by 5 mg/kg on days 2-5) was compared to amoxicillin/clavulanate potassium (4:1). For the 553 patients who were evaluated for clinical efficacy, the clinical success rate (i.e., cure plus improvement) at the day 11 visit was 88% for azithromycin and 88% for the control agent. For the 528 patients who were evaluated at the day 30 visit, the clinical success rate was 76% for azithromycin and 76% for the control agent.
Protocol 2
In a non-comparative clinical and microbiologic trial performed in North America and in which significant numbers of β-lactamase producing organisms were identified (35%), the combined clinical success rate (i.e., cure plus improvement) was 84% at the day 11 visit (n=131) and 70% at the day 30 visit (n=122).
Microbiologic determinations were made at the pre-treatment visit. Microbiology was not reassessed at later visits. The following presumptive bacterial/clinical cure outcomes (i.e., clinical success) were obtained from the evaluable group:
| Presumed Bacteriologic Eradication Clinical Success | Day 11 | Day 30 | ||
| Azithromycin | Azithromycin | |||
S. pneumoniae H. influenzae M. catarrhalis S. pyogenes | 61/74 (82%) 43/54 (80%) 28/35 (80%) 11/11 (100%) | 40/56 (71%) 30/47 (64%) 19/26 (73%) 7/7 | ||
| Overall | 177/217 (82%) | 97/137 (73%) | ||
From the perspective of evaluating clinical trials in patients using the 3 day or 1 day accelerated regimen of azithromycin, the analysis of efficacy was based on a Modified Intent to Treat population with efficacy assessments at approximately Day 11-16 and Day 28-32. Since peak age incidence for acute otitis media is 6-18 months of age, stratified data is provided for clinical guidance in this age group.
Efficacy using azithromycin 30 mg/kg given over 3 days
Protocol 3
In a double-blind, controlled, randomized clinical study of acute otitis media in North American children from 6 months to 12 years of age, azithromycin (10 mg/kg per day for 3 days) was compared to amoxicillin/clavulanate potassium (7:1) in divided doses q12h for 10 days. Each child received active drug and placebo matched for the comparator. For the 366 patients who were evaluated for clinical efficacy, the clinical success rate (i.e., cure plus improvement) at the day 12 visit was 83% for azithromycin and 88% for the control agent. For the 362 patients who were evaluated at the day 24-28 visit, the clinical success rate was 74% for azithromycin and
69% for the control agent.
Protocol 3 MITT Subjects < 2years of age | Azithromycin 3 day 10mg/kg/day N (%) | Comparator N (%) |
| Evaluable at Day 12 | 60 | 52 |
| Cure | 23 (38%) | 29 (56%) |
| Improvement | 22 (37%) | 15 (29%) |
| Failure | 15 (25%) | 8 (15%) |
| Evaluable at Day 24-28 | 58 | 52 |
| Cure | 35 (60%) | 30 (58%) |
| Improvement | 0 (0%) | 0 (0%) |
| Failure | 23 (40%) | 22 (42%) |
Efficacy using azithromycin 30 mg/kg given as a single dose
Protocol 4
In a double-blind, controlled, randomized clinical study of acute otitis media in North American children from 6 months to 12 years of age, azithromycin (given at 30mg/kg as a single dose on day 1) was compared to amoxicillin/clavulanate potassium (7:1) in divided doses q12h for 10 days. Each child received active drug, and placebo matched for the comparator. For the 321 subjects who were evaluated at Day 12-16, the clinical success rate (cure plus improvement) was 87% for azithromycin, and 88% for the comparator. For the 305 subjects who were evaluated at Day 28-32, the clinical success rate was 75% for both azithromycin and the comparator.
Protocol 4 MITT subjects < 2 years | Azithromycin 1 day N (%) | Comparator N (%) |
| Evaluable at Day 12-16 | 68 | 56 |
| Cure | 36 (53%) | 39 (70%) |
| Improvement | 17 (25%) | 6 (11%) |
| Failure | 15 (22%) | 11 (20%) |
| Evaluable at Day 28-32 | 64 | 53 |
| Cure | 40 (63%) | 27 (51%) |
| Improvement | 1 (1.5%) | 3 (6%) |
| Failure | 23 (36%) | 23 (43%) |
Protocol 5
Protocol 5 MITT subjects < 2 years | Azithromycin 1 day N (%) |
| Evaluable at Day 10 | 82 |
| Cure | 50 (61%) |
| Improvement | 19 (23%) |
| Failure | 13 (16%) |
| Evaluable at Day 24-28 | 83 |
| Cure | 64 (77%) |
| Improvement | 0 (0%) |
| Failure | 19 (23%) |
| Day 10 | Day 24-28 | ||||||||||
Presumed Bacteriologic Eradication/ Clinical Success | MITT | MITT < =2years | MITT | MITT <=2years | |||||||
| S. pneumoniae | 70/76 (92%) | 23/25 (92%) | 67/76 (88%) | 20/25 (80%) | |||||||
| H. influenzae | 30/42 (71%) | 11/18 (61%) | 28/44 (64%) | 10/19 (53%) | |||||||
| M. catarrhalis | 10/10 (100%) | 6 /6 (100%) | 10/10 (100%) | 6/6 (100%) | |||||||
| Overall | 110/128 (86%) | 40/49 (82%) | 105/130 (81%) | 36/50 (72%) | |||||||
In a non-comparative clinical and microbiological trial enrolling 70% North American children and 30% South American children, 248 patients from 6 months to 12 years of age with documented acute otitis media were dosed with a single oral dose of azithromycin (30 mg/kg on day 1). For the 240 evaluable patients, the clinical success rate (i.e., cure plus improvement) at day 10 was 89% and for the 242 patients evaluable at day 24-28, the clinical success rate (cure) was 85%. Of the 76 S. pneumoniae isolates, 16% exhibited resistance to azithromycin at baseline. No bacterial eradication data is available for the azithromycin 3 day regimen.
Pharyngitis and Tonsillitis:
Efficacy using azithromycin 60 mg/kg over 5 days
In three double-blind North American controlled studies, azithromycin (12 mg/kg once a day for 5 days) was compared to penicillin V (250 mg three times a day for 10 days) in the treatment of pharyngitis due to documented group A β-hemolytic streptococci (GAβHS or S. pyogenes). Azithromycin was clinically and microbiologically statistically superior to penicillin at day 14 and day 30 with the following clinical success (i.e., cure and improvement) and bacteriologic efficacy rates (for the combined evaluable patients with documented GaβHS):
3 Combined Streptococcal Pharyngitis Studies
5-Day Dosing Regimen
Azithromycin vs. Penicillin V
EFFICACY RESULTS
| Day 14 | Day 30 | |||
| Bacteriologic Eradication | ||||
Azithromycin Penicillin V | 323/340 (95%) 242/332 (73%) | 261/329 (79%) 214/304 (71%) | ||
| Clinical Success (Cure plus improvement) | ||||
Azithromycin Penicillin V | 336/343 (98%) 284/338 (84%) | 313/328 (95%) 240/303 (79%) | ||
Approximately 1% of azithromycin-susceptible S. pyogenes isolates were resistant to azithromycin following therapy.
Adult Patients
Acute Bacterial Exacerbations of Chronic Bronchitis:
Efficacy using azithromycin 500 mg over 3 days
In a randomized, double-blind controlled clinical trial of acute exacerbation of chronic bronchitis (AECB) in 404 adult patients, azithromycin (500 mg once daily for 3 days) was compared with clarithromycin (500 mg twice daily for 10 days). The primary endpoint of this trial was the clinical cure rate at Day 21- 24. For the 377 patients analyzed in the MITT analysis at the Day 21-24 visit, the clinical cure rate for 3 days of azithromycin was 87% (162/186) compared to 85% (162/191) for 10 days of clarithromycin (95% CI for azithromycin-clarithromycin cure rate = -5.3, 9.8).
The following outcomes were the clinical cure rates at the Day 21-24 visit for the bacteriologically evaluable patients by pathogen:
| Clinical Outcome by Baseline Pathogen | ||
| Pathogen | Azithromycin (3 days) | Clarithromycin (10 days) |
| S. pneumonia | 29/32 (91%) | 21/27 (78%) |
| H. influenza | 12/14 (86%) | 14/16 (88%) |
| M. catarrhalis | 11/12 (92%) | 12/15 (80%) |
DETAILED PHARMACOLOGY
Following oral administration, azithromycin is rapidly absorbed (Tmax = 2-3 hours) and distributed widely throughout the body. Rapid movement of azithromycin from blood into tissue results in significantly higher azithromycin concentrations in tissue than in plasma (up to 50 times the maximum observed concentration in plasma). The absolute bioavailability is approximately 37%.
Adults:
Following administration of a 500 mg oral dose, the maximum serum concentration (Cmax) is 0.4 µg/mL and is attained 2-3 hours after dosing with areas under the curve of 2.6 µg·hr/mL (AUC 0-24) and 3.7 µg·hr/mL (AUC 0-48) and trough levels of 0.05 µg/mL. These oral values are approximately 38%, 83% and 52% of the values observed following a single 500 mg I.V. 3-hour infusion: Cmax 1.08 µg/mL, trough level 0.06 µg/mL, and AUC24 5.0 µg·hr/mL. Thus, plasma concentrations are higher following the intravenous regimen throughout the 24-hour interval. Also refer to tabulated pharmacokinetic data reported in adults under ACTION AND CLINICAL PHARMACOLOGY, Adult Pharmacokinetics section. When studied in healthy elderly subjects from age 65 to 85 years, the pharmacokinetic parameters of azithromycin in elderly men were similar to those in young adults; however, in elderly women, although higher peak concentrations (increased by 30 to 50%) were observed, no significant accumulation occurred.
The pharmacokinetic parameters of azithromycin in plasma, after a loading dose of 500 mg on day 1 followed by 250 mg q.d. on days 2 through 5 in healthy young adults (age 18-40 years old) are presented in the following table:
Pharmacokinetic Parameters (Mean) in Adult Subjects (Total n=12) on Days 1 and 5*
| Day 1 | Day 5 | |
| Cmax (µg/mL) | 0.41 | 0.24 |
| Tmax (h) | 2.5 | 3.2 |
| AUC0-24 (µg • h/mL) | 2.6 | 2.1 |
| Cmin (µg/mL) | 0.05 | 0.05 |
| Urinary Excret. (% dose) | 4.5 | 6.5 |
2 x 250 mg on Day 1 followed by one 250 mg on Days 2 through 5
In this study, there was no significant difference in the disposition of azithromycin between male and female subjects. Plasma concentrations of azithromycin declined in a polyphasic pattern resulting in an average terminal half-life of 68 hours. With this regimen, Cmin and Cmax remained essentially unchanged from day 2 through day 5 of therapy. However, without a loading dose, azithromycin Cmin levels required 5 to 7 days to reach steady-state.
In a two-way crossover study, 12 adult normal volunteers (6 males; 6 females) received 1500 mg of azithromycin, administered in single daily doses over either 5 days (two 250 mg tablets on day 1, followed by one 250 mg tablet on days 2-5) or 3 days (500 mg per day). Mean peak serum concentrations were similar on day 1 for both regimens and slightly higher on days 2 and 3 for the 3-day regimen, suggesting that there is minimal serum accumulation of azithromycin on days 2 and 3 of the 3-day regimen.
| Pharmacokinetic Parameter (mean) | 3-Day Regimen | 5-Day Regimen | |||||||||
| Day 1 | Day 2 | Day 3 | Day 1 | Day 5 | |||||||
| Cmax (serum, µg/mL) | 0.310 | 0.446 | 0.383 | 0.290 | 0.182 | ||||||
| Serum AUC0-∞ ( µg.hr/mL) | 15.2 | 14.5 | |||||||||
| Kel (hr-1) | 0.0101 | 0.0105 | |||||||||
| Serum T1/2 | 68.6 hr | 66.0 hr | |||||||||
Mean AUC0-∞ for both regimens were similar, with a ratio of AUC0-∞(3-day)/AUC0-∞(5-day) of 105% (90% CI=93, 120). Serum concentrations of azithromycin declined in a polyphasic pattern resulting in average terminal half-life of 68.6 hours for the 3-day regimen and about 66 hours for the 5-day regimen.
Median azithromycin exposure (AUC0-288) in mononuclear (MN) and polymorphonuclear (PMN) leukocytes following either the 5-day or 3-day regimen was more than 1000-fold and 800-fold greater than in serum, respectively. Administration of the same total dose with either the 5-day or 3-day regimen may be expected to provide comparable concentrations of azithromycin with MN and PMN leukocytes.
The table below compares pharmacokinetic parameters following single oral doses of 500 mg azithromycin with those obtained after a single 500 mg I.V. 3-hour infusion.
Pharmacokinetic parameters in adults after oral and intravenous administration of 500 mg azithromycin | |||
| Cmax (µg/mL) | trough level (µg/mL) | AUC0-24 (µg⋅ h/mL) | |
| 500 mg single oral dose | 0.41 | 0.05 | 2.5 |
| 500 mg I.V. infusion over 3 hours | 1.08 | 0.06 | 5 |
Thus, plasma concentrations are higher following the intravenous regimen throughout the 24-hour interval. Although tissue levels have not been obtained following intravenous infusions of azithromycin, these data suggest that they would be substantially greater than those observed following oral administration.
After oral administration, serum concentrations of azithromycin decline in a polyphasic pattern, resulting in an average terminal half-life of 68 hours.
The high values for apparent steady-state volume of distribution (31.1 L/kg) and plasma clearance (630 mL/min) suggest that the prolonged half-life is due to extensive uptake and subsequent release of drug from tissues. The tissue (or fluid) to plasma concentration ratios for key sites of infection are shown in the following table:
| Azithromycin Concentrations Following the Recommended Clinical Dosage Regimen of 500 mg (2 x 250 mg) on Day 1 Followed by 250 mg Daily for Four Additional Days | ||||
| Tissue or Fluid | Sample Time after Final Dose (hrs) | Tissue or Fluid µg/g or µg/mL | Plasma/Serum µg/mL | Concentration Ratio |
| Skin | 72 | 0.42 | 0.011 | 38.2 |
| Lung | 72 | 4.05 | 0.011 | 368.2 |
| Sputum* | 15 | 3.7 | 0.1 | 37 |
| Tonsil** | 9-18 180 | 4.5 0.93 | 0.03 0.006 | 150 155 |
| Cervix *** | 19 | 2.8 | 0.04 | 70 |
* Samples were obtained 2-24 hours after the first dose
** Dosing regimen of 2 doses of 250 mg each, separated by 12 hours
*** Sample was obtained 19 hours after a single 500 mg dose
The extensive tissue distribution is confirmed by examination of other tissues (prostate; ovary, uterus and salpinx; stomach; liver and gallbladder), in which azithromycin is present in concentrations of 2 µg/g tissue or greater. However, only very low concentrations are noted in cerebrospinal fluid (less than 0.01 µg/mL) of noninflamed meninges. High tissue concentrations should not be interpreted to be quantitatively related to clinical efficacy.
When azithromycin oral suspension as the 200 mg/5mL dose was administered with food to 28 adult healthy male subjects, the rate of absorption (Cmax) was increased by 56% while the extent of absorption (AUC) was unchanged.
The extent of absorption is unaffected by co-administration with antacid; however, the Cmax is reduced by 24%. Administration of cimetidine (800 mg) two hours prior to azithromycin had no effect on azithromycin absorption. There is no evidence of any pharmacokinetic interaction when azithromycin and theophylline are administered to healthy volunteers.
Azithromycin did not affect the prothrombin time response to a single dose of warfarin (15 mg).
However, prudent medical practice dictates careful monitoring of prothrombin time in all patients.
The serum protein binding of azithromycin is variable in the concentration range approximating human exposure, decreasing from 51% at 0.02 µg/mL to 7% at 2 µg/mL. These values are not likely to be high enough to influence the protein binding of other drugs or to cause significant protein binding interactions with other drugs.
Following a five-day dosing regimen, human bile contains concentrations of azithromycin much greater (approximately 200 µg/mL) than those in serum (<0.1 µg/mL), indicating that biliary excretion of azithromycin is a major route of elimination. The major portion of the drug-related material in bile is unchanged drug. Approximately 6% of the administered dose appears in urine.
In patients with mild to moderate hepatic impairment, there is no evidence of marked change in serum pharmacokinetics of azithromycin compared to those with normal hepatic function. In these patients urinary recovery of azithromycin appears to increase.
Comparison of the pharmacokinetics of azithromycin immediate-release oral formulations and regimens and azithromycin sustained-release granules.
The bioavailability of a single 2 g dose of azithromycin sustained release relative to a single 2 g dose of azithromycin immediate-release (powder for oral suspension) was 83%; peak serum concentration was lower by 57% and was achieved approximately 2.5 hours later following azithromycin sustained release administration. Thus, a single 2 g dose of azithromycin sustained release is not bioequivalent and is not interchangeable with a single 2 g dose of azithromycin immediate-release (tablets or powder for oral suspension).
Serum pharmacokinetic parameters for a single 2 g azithromycin sustained release dose, from a study in healthy adult subjects, are shown in the following table alongside data for 3- and 5-day azithromycin immediate-release tablet regimens from a separate clinical study in healthy adult subjects. The data from these two studies suggest that higher peak serum concentration (Cmax) and greater systemic exposure (AUC) of azithromycin are achieved on the day of dosing following a single 2 g dose of azithromycin sustained-release granules compared to dosing with conventional immediate-release formulations (1.5 g of azithromycin tablets administered over 3 days (500 mg/day) or 5 days (500 mg on day 1, 250 mg/day on days 2-5). Consequently, due to a different pharmacokinetic profile, azithromycin sustained release is not bioequivalent to and is not interchangeable with azithromycin immediate-release tablet 3-day or 5-day dosing regimens.
Mean (SD) Serum Pharmacokinetic Parameters for Azithromycin on Day 1 Following the Administration of a Single Dose of 2 g Azithromycin Sustained Release or 1.5 g of Azithromycin Immediate-release Tablets Given over 3 Days (500 mg/day) or 5 Days (500 mg on Day 1 and 250 mg on Days 2-5) to Healthy Adult Subjects
| Pharmacokinetic Parameter1 | Azithromycin Regimen | ||
|---|---|---|---|
| Azithromycin Sustained Release [N=41]2 | Azithromycin Immediate Release 3-day3 [N=12] | Azithromycin Immediate Release 5-day3 [N=12] | |
| Cmax (µg/mL) | 0.821 (0.281) | 0.441 (0.223) | 0.434 (0.202) |
| Tmax4 (hr) | 5.0 (2.0-8.0) | 2.5 (1.0-4.0) | 2.5 (1.0-6.0) |
| AUC0-24 (µg·hr/mL) | 8.62 (2.34) | 2.58 (0.84) | 2.60 (0.71) |
| AUC0-∞5 (µg·hr/mL) | 20.0 (6.66) | 17.4 (6.2) | 14.9 (3.1) |
| t1/2 (hr) | 58.8 (6.91) | 71.8 (14.7) | 68.9 (13.8) |
N = no. of subjects studied SD = standard deviation Cmax = maximum serum concentration Tmax = time to Cmax AUC = area under concentration vs. time curve t1/2 = terminal serum half-life 1 Azithromycin sustained release data and data for azithromycin immediate-release 3-day and 5-day regimens were obtained from two separate pharmacokinetic studies 2 N = 21 for AUC0-∞ and t1/2 3 Cmax, Tmax and AUC0-24 values for Day 1 only 4 Median (range) 5 Total AUC for the 1-day, 3-day and 5-day regimens | |||
Children:
When azithromycin was dosed at 10 mg/kg day 1, followed by 5 mg/kg days 2 through 5 in children 1 to 15 years old, the mean pharmacokinetic parameters on day 5 were:
Pharmacokinetic parameters in pediatric subjects on day 5
at dosage 10 mg/kg (day 1) and 5 mg/kg (days 2-5)*
| Age 1-5 | Age 5-15 | ||||
Cmax (µg/mL) | Tmax (hrs) | AUC0-24 (µg•hr/mL) | Cmax (µg/mL) | Tmax (hrs) | AUC0-24 (µg•hr/mL) |
| 0.216 | 1.9 | 1.822 | 0.383 | 2.4 | 3.109 |
* Dose administered as Powder for Oral Suspension
Two clinical studies were conducted in 68 children aged 3-16 years with pharyngitis/tonsillitis to determine the pharmacokinetics and safety of azithromycin for oral suspension in children when given 60 mg/kg in divided doses over either 3 or 5 days.
Both studies were open, non-comparative trials. Drug was administered following a low-fat breakfast in order to assess the effect of food on absorption and safety.
The first study consisted of 35 pediatric subjects treated with 20 mg/kg/day (maximum daily dose of 500 mg) for 3 days of whom 34 subjects were evaluated for pharmacokinetics.
In the second study, 33 pediatric subjects received doses of 12 mg/kg/day (maximum daily dose of 500 mg) for 5 days of whom 31 subjects were evaluated for pharmacokinetics.
In both studies, azithromycin levels were determined over a 24-hour period following the last daily dose. Subjects weighing above 25.0 kg in the 3-day study or 41.7 kg in the 5-day study received the maximum adult daily dose of 500 mg. Eleven subjects (weighing 25.0 kg or less) in the first study and 17 subjects (weighing 41.7 kg or less) in the second study received a total dose of 60 mg/kg. The following table shows pharmacokinetic data in the subset of children who received a total dose of 60 mg/kg.
3-Day Regimen (20mg/kg x 3 days) | 5-Day Regimen (12 mg/kg x 5 days) | ||||||||
| n | 11 | 17 | |||||||
| Cmax (µg/mL) | 1.05 ± .44a | 0.534 ± 0.361a | |||||||
| Tmax (hr) | 3 ± 2.0a | 2.2 ± 0.8a | |||||||
| AUC0-24(µg _hr/mL) | 7.92 ± 2.87a | 3.94 ± 1.90a | |||||||
| a Arithmetic means | |||||||||
Single dose pharmacokinetics in children given doses of 30 mg/kg has not been studied.
MICROBIOLOGY
Mechanism of Resistance:
The two most frequently encountered mechanisms of resistance to macrolides, including azithromycin, are target modification (most often by methylation of 23S rRNA) and active efflux. The occurrence of these resistance mechanisms varies from species to species and, within a species, the frequency of resistance varies by geographical location.
Spectrum of Activity:
Azithromycin has been shown to be active against most isolates of the following microorganisms, both in vitro and in clinical infections as described in the INDICATIONS SECTION.
Gram-positive bacteria
Staphylococcus aureus
Streptococcus agalactiae
Streptococcus pneumoniae
Streptococcus pyogenes
Gram-negative bacteria
Haemophilus ducreyi
Haemophilus influenzae
Moraxella catarrhalis
Neisseria gonorrhoeae
“Other” bacteria
Chlamydophila pneumoniae
Chlamydia trachomatis
Mycoplasma pneumoniae
The following in vitro data are available, but their clinical significance is unknown.
At least 90% of the following bacteria exhibit an in vitro minimum inhibitory concentration MIC) less than or equal to the azithromycin susceptible breakpoint of ≤ 4mcg/mL. However, safety and effectiveness of azithromycin in treating clinical infections due to these bacteria have not been established in adequate and well-controlled trials.
Gram-positive bacteria
Beta-hemolytic streptococci (Groups C, F, G)
Viridans group streptococci
Gram-negative bacteria
Bordetella pertussis
Anaerobic bacteria
Peptostreptococcus species
Prevotella bivia
“Other” bacteria
Ureaplasma urealyticum
Legionella pneumophila
Mycoplasma hominis
Susceptibility Testing Methods:
When available, the results of in vitro susceptibility test results for antimicrobial drugs used in resident hospitals should be provided to the physician as periodic reports which describe the susceptibility profile of nosocomial and community-acquired pathogens. These reports may differ from susceptibility data obtained from outpatient use, but could aid the physician in selecting the most effective antimicrobial.
Dilution Techniques:
Quantitative methods are used to determine antimicrobial minimum inhibitory concentrations
(MICs). These MICs provide estimates of the susceptibility of bacteria to antimicrobial compounds. The MICs should be determined using a standardized procedure. Standardized procedures are based on a dilution method54,52 (broth or agar) or equivalent with standardized inoculum concentration and standardized concentration of azithromycin powder. The MIC values should be interpreted according to criteria provided in Table 1.
Diffusion Techniques:
Quantitative methods that require measurement of zone diameters also provide reproducible estimates of the susceptibility of bacteria to antimicrobial compounds. One such standardized procedure52, 53 requires the use of standardized inoculum concentration. This procedure uses paper disks impregnated with 15-mcg azithromycin to test the susceptibility of bacteria to azithromycin. The disk diffusion interpretive criteria are provided in Table 1.
Table 1. Susceptibility Interpretive Criteria for Azithromycin
Susceptibility Test Result Interpretive Criteria
| Pathogen | Minimum Inhibitory Concentrations (mcg/mL) | Disk Diffusion (zone diameters in mm) | ||||
| S | I | R | S | I | R | |
| Haemophilus influenzaea. | ≤ 4 | -- | -- | ≥ 12 | -- | -- |
| Staphylococcus aureus | ≤ 2 | 4 | ≥ 8 | ≥ 18 | 14 – 17 | ≤ 13 |
Streptococci including S. pneumoniae | ≤ 0.5 | 1 | ≥ 2 | ≥ 18 | 14 – 17 | ≤ 13 |
Susceptibility to azithromycin must be tested in ambient air.
aInsufficient information is available to determine Intermediate or Resistant interpretive criteria
The ability to correlate MIC values and plasma drug levels is difficult as azithromycin concentrates in macrophages and tissues.
A report of “susceptible” indicates that the pathogen is likely to be inhibited if the antimicrobial compound reaches the concentrations usually achievable. A report of “intermediate” indicates that the result should be considered equivocal, and, if the microorganism is not fully susceptible to alternative, clinically feasible drugs, the test should be repeated. This category implies possible clinical applicability in body sites where the drug is physiologically concentrated or in situations where high dosage of drug can be used. This category also provides a buffer zone which prevents small uncontrolled technical factors from causing major discrepancies in interpretation. A report of “resistant” indicates that the pathogen is not likely to be inhibited if the antimicrobial compound reaches the concentrations usually achievable; other therapy should be selected.
Quality Control
Standardized susceptibility test procedures require the use of laboratory controls to monitor and ensure the accuracy and precision of supplies and reagents used in the assay, and the techniques of the individual performing the test. Standard azithromycin powder should provide the following range of MIC values noted in Table 2. For the diffusion technique using the azithromycin 15 mcg disk, the criteria in Table 2 should be achieved.
Table 2. Acceptable Quality Control Ranges for Azithromycin
| QC Strain | Minimum Inhibitory Concentrations (mcg/mL) | Disk Diffusion (zone diameters in mm) |
Haemophilus influenza ATCC* 49247 | 1.0 – 4.0 | 13 – 21 |
Staphylococcus aureus ATCC 29213 | 0.5 – 2.0 | --- |
Staphylococcus aureus ATCC 25923 | --- | 21 – 26 |
Streptococcus pneumonia ATCC 49619 | 0.06 – 0.25 | 19 – 25 |
Susceptibility to azithromycin must be tested in ambient air.
*ATCC = American Type Culture Collection
TOXICOLOGY
Acute Toxicity: Mice and Rats
| Oral and Intraperitoneal Toxicity Studies in Mice and Rats | |||
| Route | Species | Sex | LD50 (mg of free base/kg) |
| Oral | Mice | M | 3000 |
| Oral | Mice | F | 4000 |
| Oral | Rats | M | >2000 |
| Oral | Rats | F | >2000 |
| Oral | Neonatal Rats | M | >1000 |
| Oral | Neonatal Rats | F | >1000 |
| I/P | Mice | M | >400 <600 |
| I/P | Mice | F | NA* |
| I/P | Rats | M | >500 <900 |
| I/P | Rats | F | NA* |
* NA = not available
Adult animals (Mice and Rats)
Most mortality occurred within 1 to 2 hours and generally within 48 hours of dosing. At higher doses in mice, symptomatology included clonic convulsive activity, loss of righting reflex, gasping, and blanching prior to death.
Gross necropsy of mice or rats which died following intraperitoneal doses revealed yellowish or clear fluid in the pleural and peritoneal cavities. At necropsy on day 14 there were no gross pathological changes in either species aside from a few liver adhesions to the diaphragm.
Neonatal animals (Rats)
No deaths or remarkable clinical signs were observed in any animal during the 14-day observation period. All animals gained weight during the trial. At sacrifice on day 15, no remarkable gross findings were observed in any surviving rat.
Subacute Toxicity:
Phospholipidosis has been observed in animals administered high doses of azithromycin. This effect is reversible after cessation of azithromycin treatment in animals. Despite light- and electron-microscopic correlates of phospholipidosis (myeloid figures and intracytoplasmic vacuoles) in many organs, only in dogs receiving 100 mg/kg/day for at least 2 months have kidney, liver, and gallbladder toxicity been seen. This dose in dogs results in tissue levels greater than 5000 mg/g. Minimal increases in serum transaminase levels in rats and dogs at 20 mg/kg/day and above have also been seen, but are consistent with findings previously reported for erythromycin. Special attention has been given to the effects of phospholipidosis in the retina, including studies of azithromycin, 30 and 100 mg/kg/day for 6 and 2 months, respectively, in dogs. No evidence was elicited of deleterious effects of azithromycin on vision, pupillary reflex or retinal vasculature. The detection of phospholipidosis in the choroid plexus and dorsal root ganglion was not associated with degenerative or functional changes.
In animal studies, treatment with azithromycin is associated with accumulation in various tissues, including the extra-cranial neural ganglia (i.e., retina and sympathetic nervous system). Tissue accumulation is both dose and time dependent, and is associated microscopically with the development of phospholipidosis (intra-lysosomal drug phospholipid complexes). The only evidence in animals that azithromycin is associated with alterations of intracellular phospholipid metabolism has been the documentation of small increases in phospholipid content after prolonged treatment (6 months) or exaggerated doses. Phospholipidosis has been observed at total cumulative doses only 2 multiples of the clinical dose. One month after withdrawal of treatment the concentration of azithromycin and the presence of phospholipidosis in tissue, including the retina, is at or near predose levels.
Subacute and Chronic Toxicity:
| SPECIES | ROUTE | DOSE mg/kg/day | ANIMALS PER DOSE LEVEL | DURATION | FINDINGS |
|---|---|---|---|---|---|
| ORAL in Adult Animals | |||||
Rat (Adult) | Oral (gavage) | 50100200 | 10/sex | 36 days + reversibility | Cecal enlargement was dose-related. Elevated serum hepatic enzyme (SGPT, SGOT, SDH, and 5'NT) levels were dose- and time-related at high and mid levels; marginal SGPT elevations only were observed in 2 rats at the low dose. Histological examination of tissues from 6/sex of mid- and high-dose and 10/sex of low-dose rats revealed evidence of phospholipidosis in bile ducts (8/20, 12/12, 12/12 low-, mid-, and high-dose rats, respectively) and hepatocytes (10/12 high dose only), fatty change (4/20, 10/12, 11/12 in low-, mid-, and high-doses, respectively), and necrosis of single hepatocytes (6/12 and 11/12, respectively, in mid- and high-dose only). Phospholipidosis also occurred in high-dose rats in the tubular cells of the renal medulla 12/12, spleen 2/12, thymus 2/12, and choroid plexus 10/12; 3/12 rats at 100 mg/kg and 10/12 at 200 mg/kg exhibited mesenteric sinusoidal lymph node phospholipidosis. Phospholipidosis is characterized by accumulation of drug-lipid complexes in lysosomes where they form ultramicroscopic lamellated structures typified at the microscopic level by vacuolated macrophage or tissue cells. The remaining animals (4/sex in control, mid- and high-dose groups) were sacrificed 20 days after termination of treatment. Phospholipidosis was still observable in the renal tubules of 7/8 high dose animals and in 1/8 mid-dose animals and in the bile duct of 1/8 high-dose animals. Fatty change was still detectable in livers of 5/8 and 6/8 mid- and high-dose animals, respectively. Megaceca also regressed following drug withdrawal. |
Dog (Adult) | Oral (gavage) | 2550100 | 3/sex | 36 days | Transaminase levels (SGPT, SGOT) were elevated in a dose-related pattern at the 2 higher doses. ALP (alkaline phosphatase), gamma-GTP, and SDH elevations occurred only at the high dose. Histological examination of tissues revealed the presence of phospholipidosis in all treated animals. It occurred in six or more organs in all 100 mg/kg/day animals. These included kidney, liver, spleen, gallbladder, thymus, mesenteric lymph node, esophagus, uterus and cervix as well as lymphatic nodules of gastrointestinal tissues. At the low dose of 25 mg/kg |
| SPECIES | ROUTE | DOSE mg/kg/day | ANIMALS PER DOSE LEVEL | DURATION | FINDINGS |
|---|---|---|---|---|---|
| phospholipidosis was confined to the spleen, gallbladder, thymus, mesenteric lymph node and the lymphatic nodules of the ileum and colon. | |||||
Rat (Adult) | Oral (gavage) | 40 (10 days on 10 days off) 0 continuous 10 " 20 " | 15/sex 25/sex | 190-193 days + reversibility | Sporadic mild elevations in SGOT and SGPT occurred in all dose groups during and after the treatment period. There was no evidence of phospholipidosis. |
Dog (Adult) | Oral (gavage) | 40 (10 days on 10 days off) 0 10 20 | 4/sex 4/sex + 2/sex + 2/sex | 190 days + reversibility 1 month 2 months | Sporadic elevations in SGPT levels occurred at 20 and 40 mg/kg only. Phospholipidosis, was minimal to mild in the kidney, liver, gallbladder, spleen, mesenteric lymph node, esophagus and prostate of almost all 40 and 20 mg/kg dogs. In dogs dosed for 6 months at 20 mg/kg/day complete reversibility of phospholipidosis of the kidney, liver, and spleen with minimal phospholipidosis still present in the gallbladder and esophagus was demonstrated in the animals sacrificed 2 months after the end of treatment. |
Dog (Adult) | Oral (gavage) | 30100 | 6/sex | 6 months 2 months + reversibility | Selected animals were sacrificed at end of treatment; sacrifices (1/sex/dose level) were also performed 1 month (100 mg/kg), 2 months (30 mg/kg) and 4 months (100 mg/kg) post-treatment. Necropsies of the remaining animals were performed 7 months (30 mg/kg) and 11 months (100 mg/kg) post treatment. Drug treatment of high dose dogs was terminated at 2 months (61 doses) due to intolerance. Serum chemistry changes including substantial increases in liver enzymes (SGPT, SGOT, ALP, SDH, gamma-GPT) and BUN as well as mild decreases in erythrocytic parameters (RBC, Hb, Hct) and the presence of atypical eosinophil and vacuolated lymphocytes returned to normal range within 2 months of withdrawal from treatment. The low dose was well tolerated. Dose-related effects on tapetum lucidum reflectivity ranged from trace (low dose) to moderate (high dose) decoloration, dulled reflectivity and loss of the tapetum-choroid junctional zone. Following cessation of treatment, most animals showed improvements in these ocular changes. Normal junctional tissue was evident in high dose animals 4 months after withdrawal. At no time was there |
| SPECIES | ROUTE | DOSE mg/kg/day | ANIMALS PER DOSE LEVEL | DURATION | FINDINGS |
|---|---|---|---|---|---|
ophthalmoscopic evidence of an effect on vision. Histological examination at the end of treatment showed phospholipidosis. In the eye it included the tapetum, neurons of the retinal ganglion cell, inner nuclear, inner and outer plexiform layers, and mural pericytes of the superficial retinal vasculature. The rod and cone segments and retinal pigmented epithelium were generally spared. Also affected were dorsal root ganglion, liver, gallbladder, kidneys, spleen and pancreas and, at the high dose only gastrointestinal tract, mesenteric lymph nodes, thymus, aorta, heart, salivary gland and lung. Dose-related degenerative changes were observed only in the liver (focal necrosis of hepatocytes and bile duct epithelium), gallbladder (hyperplasia) and kidneys (glomerulonephrosis). All of the above effects, with the exception of those on the retina, dorsal root ganglion and gallbladder which all abated in severity, were completely reversible on drug withdrawal from both low and high dose animals. In general, these changes were consistent with the relative drug/tissue concentrations attained and their decline following withdrawal. Biochemical measurements of spleen, liver, kidney and retinal phospholipids of animals treated with 30 mg/kg drug for 6 months showed a difference from control only for the spleen, the tissue with the highest drug concentration. This experiment demonstrates that drug-induced phospholipidosis, although dose-dependent in tissue distribution and intensity, does not represent a toxic end point per se but is responsible for the cumulative tissue deposition of azithromycin. | |||||
Dog (Adult) | Oral (gavage) | 30100 | 6/sex | 6 months + reversibility | Intermittent dosing: (10 days on, 10 days off drug) for: 5 months (100 mg), 6 months (30 mg). This experiment demonstrates that intermittent administration (to mimic a hypothetical clinical dose regime) produced less phospholipidosis than azithromycin administered continuously. |
ORAL in Neonatal Animals Oral Subacute/Neonatal RATS | |||||
Rat (Neonatal 4 days) | Oral (gavage) | 102040 | 10/sex 10/sex | 18 days (day 4 to day 21 postpartum) 10 days (day 4 to day 13 | No treatment-related clinical signs were observed. Males given the dose of 20 mg/kg weighed significantly more than the vehicle controls on day 7 and from day 13 to sacrifice on day 22 postpartum. A slight increase in the incidence and prominence of periportal vacuolization appeared treatment related. However, the vacuolization observed in the |
| SPECIES | ROUTE | DOSE mg/kg/day | ANIMALS PER DOSE LEVEL | DURATION | FINDINGS |
|---|---|---|---|---|---|
| postpartum) | treated animals was qualitatively no different from that seen in the vehicle-treated controls. There was no histologic evidence of phospholipidosis. | ||||
Rat (Neonatal 4 days) | Oral (gavage) | 406080 | 10/sex | 18 days (day 4 to day 21 postpartum) | The purpose of this study was to determine the dose at which there was evidence of phospholipidosis. There were no clinical signs of toxicity or effects on body weight. The administration of azithromycin to neonatal rats by gavage for 18 days produced clear evidence of phospholipidosis of bile duct epithelium in a dose related manner in males and females at all dose levels. Hepatocellular vacuolation, which may also be a manifestation of phospolipidosis, was apparent in most males given azithromycin but was not observed in the vehicle-treated males. However, in the female rats, hepatocellular vacuolation was seen in the azithromycin treated animals as well as in those given the vehicle, suggesting that it does not represent phospholipidosis in this study. |
Rat (Neonatal 4 days) | Oral (gavage) | 100120140 | 10/sex | 18 days (day 4 to day 21 postpartum) | In the previous study, evidence of dose-related phospholipidosis was observed in only the bile duct epithelium of males and females at each dose. The purpose of the present study was to attempt to identify doses at which phospholipidosis is produced in more than one organ and/or tissue. There were no clinical signs of toxicity. The administration of azithromycin to neonatal rats by gavage for 18 days produced clear evidence of phospholipidosis of bile duct epithelium in all males and females at each dose. The hepatocellular vacuolation apparent in some animals from each dose was above that seen in the vehicle-treated animals and also appeared to be a manifestation of phospholipidosis. In addition, myocardial phospholipidosis was evident in a majority of high and intermediate dose males and females and in a single low dose male. |
Rat (Neonatal 4 days) | Oral (gavage) | 3070140 | 20/sex 10/sex 10/sex 20/sex | 18 days (day 4 to day 21 postpartum) and 30 Day Reversibility Period for 10/sex | The purpose of this study was to determine whether phospholipidosis, previously diagnosed by light and electron microscopic examination in neonatal animals treated with azithromycin could be confirmed biochemically by measurement of tissue phospholipid levels. All low and intermediate dose animals, plus one half of the high dose and vehicle-treated control animals were sacrificed on Day 22 postpartum. |
| SPECIES | ROUTE | DOSE mg/kg/day | ANIMALS PER DOSE LEVEL | DURATION | FINDINGS | ||
|---|---|---|---|---|---|---|---|
| in groups treated by 0 and 140 mg/kg. | The remaining rats were sacrificed on Day 52 postpartum after a 30-day reversibility period. Assays for drug in serum, liver and brain samples obtained from pups sacrificed 24 hours after the last dose revealed that the azithromycin concentrations increased with dose and were highest in the liver, lower in the brain and lowest in serum. The concentration of azithromycin in the serum, liver and brain had declined substantially when next measured 31 days after cessation of dosing of the high dose group. Azithromycin was still detectable in the liver and brain, but serum concentrations were generally below the limit of detection. Despite the high azithromycin concentrations detected in both the liver and brain at 24 hours after the last dose, the phospholipid levels in these tissues from rats given azithromycin were no greater than those of the vehicle-treated controls at both the end of the dosing period and after the one month reversibility period. The administration of azithromycin to neonatal Long-Evans rats for 18 days produced light microscopic evidence (vacuolation) of phospholipidosis in bile duct epithelium, hepatocyte cytoplasm, cardiac muscle, smooth muscle of the duodenum and uterus and in the choroid plexus. These changes, seen in the rats sacrificed on the day after the last dose (i.e., Day 22 postpartum), were evident primarily in high dose animals, and, except for the bile ducts, at a much reduced incidence in intermediate dose animals. The only histological evidence of phospholipidosis at the low dose was in the bile ducts of a single male. No light microscopic evidence of phospholipidosis was visible in the high dose animals examined following a 30 day reversibility period. It is concluded that, in spite of histological indications of phospholipidosis and high tissue concentrations of azithromycin, there was no biochemical evidence of phospholipid accumulation in affected organs (brain and liver). | ||||||
| SPECIES | ROUTE | DOSE mg/kg/day | ANIMALS PER DOSE LEVEL | DURATION | FINDINGS |
|---|---|---|---|---|---|
| Oral Subacute/Neonatal DOGS | |||||
| Dog | Oral | 103060 | 3/sex | 5 weeks | Pups were removed from their mothers 2 hrs |
| SPECIES | ROUTE | DOSE mg/kg/day | ANIMALS PER DOSE LEVEL | DURATION | FINDINGS |
|---|---|---|---|---|---|
(Neonatal 3-5 days) | (gavage) | prior to dosing and then returned to their litters immediately thereafter. They were observed daily for developmental landmarks (eye opening, upper canine tooth eruption, ear opening and when pup "leaves the pack"). Body weights were obtained daily. Blood samples for clinical pathology profiles were drawn pretest and prior to dosing on Days 14 and Days 28 or 30. Blood samples for serum drug level determinations were obtained on Days 2, 22 or 24. Ophthalmological examinations were conducted at termination of the treatment period. All dogs were anesthetized and exsanguinated on Days 35 or 37 for necropsy. Selected organs were weighed. Tissues were taken for assays of drug concentrations and for histopathological evaluation. With the exception of a possible lag in body weight gain of female pups, there were no treatment-related effects on developmental landmarks, hematology, clinical chemistry, ophthalmological findings nor upon organ weights. Mean blood concentrations of azithromycin, generally related to dose, especially at 10 and 30 mg/kg, were somewhat higher on Day 24 than on Day 2. Evidence of phospholipidosis, previously observed in other azithromycin animal studies, was detected microscopically as swollen vacuolated cells due to myelin figures, i.e., large lysosomes containing aggregates of undigested membranes. As in adult dogs, the dose related phospholipidosis was seen in selected tissues. The effects were minimal to mild at 10 mg/kg. Phospholipidosis was not observed in the brain or in liver. Other dose related lesions were swelling and vacuolation of cells of the tapetum lucidum of the eye due to tapetal rodlet swelling and dissolution, and degeneration and necrosis of epithelial cells lining the gallbladder. The latter occurred only in mid- and high dose animals. Twenty four (24) hrs after the last dose, tissue levels of drug were much higher than in serum with mean concentrations in the order of serum=brain <eye <kidney <liver=spleen. | |||
Dog (Neonatal 3-5 days) | Oral (gavage) | 103060 | 4/sex | 11 days | Two/sex/group were necropsied at the end of the dosing period. The remaining animals were maintained for an additional 1 month dose free period prior to being necropsied. There were no treatment-related effects on developmental landmarks, body weight, hematology, clinical chemistry or organ weights. Evidence of phospholipidosis (PL) was observed microscopically at the end of the treatment period in the spleen of dogs given 30 or 60 |
| SPECIES | ROUTE | DOSE mg/kg/day | ANIMALS PER DOSE LEVEL | DURATION | FINDINGS |
|---|---|---|---|---|---|
mg/kg/day and at all dose levels in the neurons of the retina and sympathetic ganglion. The incidence and severity was generally dose related. There was no evidence of PL in the liver or brain. At the end of the 1 month drug free period, the retina and sympathetic ganglion of animals given 10 mg/kg/day had no evidence of PL. PL was still evident, although at a reduced incidence and severity, at dose levels of 30 and 60 mg/kg/day. Following a 1 month drug free period, tissue concentrations of azithromycin in the liver, kidney and spleen were approximately 1.5% of those observed at the end of dosing, indicating elimination of azithromycin from these organs. The extent of elimination from the retina could not be accurately quantitated in this study. However, the reversibility of the PL in the retina would suggest that elimination was occurring. | |||||
Dog (Neonatal 3-5 days) and 25 days | Oral (gavage) | 1060 | 4/sex (3-5 days) 2/sex (25 days) | 11 days and 30 Day Recovery Period | The purpose of this study was to further characterize the absorption and elimination of azithromycin from the choroid/retina of neonatal beagle dogs. At the end of the treatment period, 2/sex from the 3-5 day old dogs and all of the older dogs were necropsied. The remaining dogs were maintained for a 1 month dose free period to further document the elimination of azithromycin from the retina. There were no treatment-related effects on developmental landmarks, body weight, hematology or clinical chemistry. Mean whole blood concentrations of azithromycin were dose related and increased between Days 2 and 11. Liver and choroid/retina of all animals contained dose related concentrations of azithromycin. In general, these were higher in the dogs 3-5 days of age. Concentrations in the choroid/retina were less than those in the previous study (WEL 90-252) and were within historical predictions, while liver concentrations were similar to previous studies and within expectations. At the end of the one month treatment free period, the tissue concentrations of azithromycin had decreased and were within expected levels. |
| INTRAVENOUS In Adult Animals | |||||
Rat (Adult) | IV | 10 20 20 (every other day) | 10/sex | 14 days | No untoward effects. |
Dog (Adult) | IV | 10 20 | 3/sex | 14 days | No untoward effects with 3 exceptions in the former two groups. |
| SPECIES | ROUTE | DOSE mg/kg/day | ANIMALS PER DOSE LEVEL | DURATION | FINDINGS |
|---|---|---|---|---|---|
| 10 (every other day) | Sporadic elevated serum liver enzyme levels in 2/3 females at the high-dose level; serum alkaline phosphatase levels gradually increased in one 10 mg/kg/day female; phospholipidosis by accumulation of vacuolated macrophages within the lamina propria of the gallbladder and germinal centers of the mesenteric lymph nodes of dogs receiving 20 mg/kg/day. | ||||
Rat (Adult) | IV | 5 10 20 | 10/sex | 1 month (36-39 days) | Minimal phospholipidosis in the epithelium of the large bile ducts was observed in all high dose and in 13/20 mid-dose animals and at the injection site in the tail of one high dose rat. |
Dog (Adult) | IV | 5 10 20 | 3/sex | 1 month (36 days) | Slight SGPT elevations occurred in 4/6 high dose animals together with a slight increase in serum alkaline phosphatase activity. Slight SGPT elevations were also noted in 1 low dose and 1 control animal. Histological changes at the high dose were limited to the presence of phospholipidosis. One 10 mg/kg dog also showed minimal phospholipidosis in the large bile ducts. There was no evidence of phospholipidosis at 5 mg/kg/day. |
| SPECIAL EXPLORATORY TOXICOLOGY | |||||
| Rat | Oral (gavage) | 10 0 40 200 chloroquine: 25 | 5/sex 10/sex 10/sex | 5 days | Animals (5/sex/group) from the 40 and 200 mg/kg azithromycin and chloroquine groups were removed from treatment for 23 days to study the effect of reversibility. No elevations in tissue phospholipid levels or hepatic necrosis were seen at any dose. Myelin figures were seen in liver, bile ducts and retinal pigmented epithelium. One chloroquine animal had a few myelin figures in retinal ganglion cells. |
| Rat | Oral (gavage) | 0 200 | 10/sex | 42 days | Phospholipid levels were significantly elevated above control in liver, kidney, spleen and lymphocytes (p<.05). |
| Dog | Oral (gavage) | 0 azithromycin: 10 40 200 chloroquine: 15 | 1/sex 2/sex 1/sex | 5 days | The livers of the 200 mg/kg azithromycin animals showed the highest drug concentration (>4000 μg/g) of any tissues in the series of experiments. This was accompanied by a 38% elevation in hepatic phospholipids, multifocal hepatic necrosis and marked accumulation of myelin figures in both hepatocytes and bile duct epithelium. Myelin figures were also seen in the liver at 40 mg/kg azithromycin (drug concentration = 817 μg/g) and with chloroquine but not with 10 mg/kg azithromycin. Azithromycin caused the formation of myelin figures in retinal ganglion cells from equivocal at 10 mg/kg to moderate at 200 mg/kg. The effect was less severe than chloroquine, 15 mg/kg, which caused a marked degree of myelin figure |
| SPECIES | ROUTE | DOSE mg/kg/day | ANIMALS PER DOSE LEVEL | DURATION | FINDINGS |
|---|---|---|---|---|---|
| formation in retinal ganglion cells. | |||||
| Dog | Oral (gavage) | 0 azithromycin: 30 erythromycin: 400 | 1/sex 2/sex 2/sex | 5 days | Reversal periods of 22 and 36 days were included for those animals treated with azithromycin (1/sex/period). Tissue phospholipids were elevated in the livers of erythromycin animals only. Myelin figures or enlarged lysosomes were seen to a minimal extent in the retinal ganglion cells, liver and choroid plexus of azithromycin animals and in the liver of erythromycin dogs. The drug concentrations were markedly reduced at the end of the reversal periods and no myelin figures remained in the liver or choroid plexus. |
| Dog | Oral (gavage) | erythromycin: 400 | 2/sex | 5 days | Dogs were necropsied immediately after the last dose. A few myelin figures were seen in the retinal ganglion cells of one animal. |
Dogs Atapetal Tapetal | Oral | azithromycin: 0 100 0 100 | 3 (2M,1F) 3 (2F, 1M) 3 (2M, 1F) 3 (2F, 1M) | 35-36 days | Ophthalmoscopic examinations revealed no changes in the atapetal dogs while tapetal decoloration, dulling of normal reflectivity and loss of color difference at the tapetal junctional zone was observed in the tapetal dogs. Light and/or electron microscopic examination of the retinas of both tapetal and atapetal dogs revealed signs of phospholipidosis in ganglion cells, the inner nuclear layer and inner and outer plexiform layers. Other changes observed in both tapetal and atapetal dogs are comparable to those observed in previous studies at the same dose. |
| SPECIAL TOXICOLOGY | |||||
| Rabbit | IM | 0 200 400 (single dose) | 3/sex | 3 days and 7 days (observation) | Signs indicative of considerable pain upon injection were produced by both volumes of the azithromycin test solution. These changes subsided within 2 to 4 days of dosing. At sacrifice 3 or 7 days post dose, substantial changes were observed in the subcutaneous tissue and the muscle. At 7 days, these changes were much smaller at 1 mL than they were at 2 mL dose. |
| Rabbit | IV | 0 10 (single dose) | 3/sex | 1 and 2 days (observation) | There were no obvious signs of pain or discomfort upon injection of normal saline with or without azithromycin in the marginal ear vein of six albino rabbits. The gross and microscopic tissue changes indicated that this solution was only minimally irritating. |
| Reproductive Studies | |||||||
|---|---|---|---|---|---|---|---|
| SPECIES | ROUTE | DOSE mg/kg/day | ANIMALS PER DOSE LEVEL | DURATION | FINDINGS | ||
| FERTILITY AND REPRODUCTIVE PERFORMANCE | |||||||
| Rat | Oral (gavage) | 0 10 20 | 15M/dose 30F/dose | 64-66 days | In females the drug given for 14 days prior to and during cohabitation (1M:2F) and to all females throughout gestation, parturition, and lactation until Day 21 postpartum resulted in a lower pregnancy rate of 63% for the high-dose group compared to 83% and 87% for the low-dose and control groups, respectively. | ||
| Rat | Oral (gavage) | 30 | 15M/dose 15F/dose | 64-66 days | In females the drug was given 15 days prior to mating and continuously throughout the 3 weeks of mating. A lower pregnancy rate for the drug-treated group (67% compared to 100% in the concurrent control group) was also found here. | ||
| FERTILITY EFFECT ON MALES OR FEMALES | |||||||
| Rat | Oral | 0 30 | 40M/dose 80F/dose (Fertile animals only) | 64 days (males) See text (females) | In females the drug was given 15 days prior to mating and continuously throughout the 3 weeks of mating. Groups were mated as follows: Group 1: Drug treated males mated with drug treated females. Group 2: Drug treated males mated with control females. Group 3: Control males mated with drug treated females. Group 4: Control males mated with control females. Pregnancy rates were: Group 1, 84%; Group 2, 89%; Group 3, 90%; and Group 4, 96%. The pregnancy rate was statistically significantly lower than control when the males and females were both treated with azithromycin (Group 1). The pregnancy rate of 84% in that group was, however, higher than in the two previous studies and well within our historical control range. The nearly identical pregnancy rates in Groups 2 and 3 (89% and 90%, respectively) do not indicate an effect on either sex alone as being the cause for the apparently reduced pregnancy rate. | ||
| Fetotoxicity Teratology | ||||||||
|---|---|---|---|---|---|---|---|---|
| SPECIES | ROUTE | DOSE mg/kg/day | ANIMALS PER DOSE LEVEL | DURATION | FINDINGS | |||
| Mice | Oral (gavage) | 0 10 20 40 | 20 | days 6-13 of gestation | Azithromycin was not toxic to the dams or their fetuses nor was there evidence of teratogenicity. | |||
| Mice | Oral (gavage) | 0 50 100 200 | 20 | days 6-13 of gestation | Azithromycin was not toxic to the dams or their fetuses nor was there evidence of teratogenicity. | |||
| Rat | Oral (gavage) | 0 10 20 40 | 20 | days 6-15 of gestation | Azithromycin was not toxic to the dams or to their fetuses nor was there evidence of teratogenicity. | |||
| Rat | Oral (gavage) | 0 50 100 200 | 20 | days 6-15 of gestation | Azithromycin was not toxic to the dams or fetuses. Dose levels of 100 and 200 mg/kg induced slight delays in maternal body weight gain and in ossification process of fetuses. The compound was neither embryotoxic nor teratogenic at the three dose levels. The 50 mg/kg dose can be considered as the no-observable-effect-level. | |||
| PERI/POSTNATAL | ||||||||
| Rat | Oral (gavage) | 102040 | 15 | See text | Azithromycin administered from day 15 p.i. through end of gestation and for the whole period of lactation was not toxic to the dams. The pre- and post-natal developments of pups were not affected. | |||
| Rat | Oral (gavage) | 0 50 100 200 | 20 | See text | Azithromycin administered from day 15 p.i. through end of gestation and for the whole period of lactation was not toxic to the dams. A slight reduction in weight gain of pups and their post-natal development was related to the litter size and not to drug administration. No drug-related external or visceral anomalies were observed. | |||
Neonatal Studies
| SPECIES | ROUTE | DOSE mg/kg/day | ANIMALS PER DOSE LEVEL | DURATION | FINDINGS |
|---|---|---|---|---|---|
| Rat | Oral | 0 10 20 40 | 10/sex | 18 days (4-21 days postpartum) 10 days (4-13 days postpartum) | There was no evidence of toxicity and no observation of phospholipidosis. |
| Rat | Oral (gavage) | 0 40 60 80 | 5/sex | 18 days (4-21 days postpartum) | Azithromycin induced dose-related microscopic evidence of phospholipidosis only in the bile duct epithelium of both males and females. |
| Rat | Oral (gavage) | 0 100 120 140 | 5/sex | 18 days (4-21 days postpartum) | Azithromycin in addition to affecting the gallbladder epithelium of all animals, induced microscopic evidence of myocardial phospholipidosis in a majority of high and intermediate dose pups as well as in a single low dose male. Hepatocellular vacuolation, apparent in some animals at each dose level, more pronounced than that of vehicle treated rats, appeared to be a manifestation of drug-induced phospholipidosis. |
| Rat | Oral (gavage) | 30700140 | 10/sex 20/sex | 18 days (4-21 days postpartum) + reversibility | Animals (treated and controls) exhibited normal growth and development. All animals at each dose were systemically exposed to azithromycin, as evidenced by the concentration of the compound in the rats' serum, liver and brain at 24 hours after the last dose. At this time point, the concentration of azithromycin in brain and especially liver greatly exceeded that in serum. At 31 days after the last dose, azithromycin is still detectable in the liver and brain of all rats in the high dose (140 mg/kg/day) reversibility group, but the serum concentrations were generally below the limit of detection (<0.01 μg/mL) and the concentration of azithromycin in the liver, brain, and serum was substantially lower than that found one day after the last dose. In spite of the high azithromycin concentrations detected in both the liver and brain at 24 hours after the last dose, the phospholipid levels in these tissues from rats given azithromycin were generally no greater than those of the vehicle-treated controls at both the end of the dosing period and after the one-month reversibility period. In the animals sacrificed the day after the last dose, i.e. on day 22 postpartum, light microscopic evidence of phospholipidosis was apparent in bile |
| SPECIES | ROUTE | DOSE mg/kg/day | ANIMALS PER DOSE LEVEL | DURATION | FINDINGS | |
|---|---|---|---|---|---|---|
duct epithelium, hepatocyte cytoplasm, cardiac muscle, smooth muscle of the duodenum and uterus, and in the choroid plexus. The only evidence of phospholipidosis at the low dose was in the bile ducts of a single male. No light microscopic evidence of phospholipidosis remained in high dose animals examined after a 30-day reversibility period. | ||||||
Carcinogenicity
Long-term toxicology studies to assess the carcinogenicity potential have not been conducted.
Genetic Toxicology
Azithromycin was examined in several genetic toxicology assays for induction of gene mutations in microbial and mammalian cells and for chromosomal mutations in vivo and in vitro. No evidence of genotoxic activity was observed in any of the following assays:
Microbial Assay: Tests were conducted on strains TA 1535, TA 1537, TA 98 and TA 100 of Salmonella typhimurium at concentrations up to 2 μg/plate (higher concentrations cause bacterial growth inhibition) in the presence and absence of Aroclor-stimulated rat or mouse liver microsomal enzymes. Additional tests were performed using the same strains of Salmonella spp. and urine from mice treated orally with up to 200 mg/kg of azithromycin.
Mammalian Cell Gene Mutation Assay: The L5178Y Mouse Lymphoma Assay for gene mutations at the thymidine kinase locus was conducted at concentrations of 36-360 μg/mL to cytotoxicity in the presence and absence of rat liver microsomal enzymes.
In Vitro Cytogenetics Assay: The clastogenic activity of azithromycin was evaluated in human lymphocytes in vitro exposed up to toxic concentrations of 40 μg/mL in the presence and 7.5 μg/mL in the absence of rat liver microsomal enzymes.
In Vivo Cytogenetics Assay: Azithromycin was examined for clastogenic activity in the bone marrow cells of male and female CD-1 mice treated orally at 200 mg/kg, and sacrificed at 6, 24 or 48 hours post-treatment.
Antigenicity Studies
Azithromycin was tested for the induction of a systemic anaphylaxis reaction in guinea pigs and in rabbits. Azithromycin did not have antigenic potential under the conditions used in the studies.
REFERENCES
|
|
|
|
|
|
|
|
|
|
|
|
|
|
|
|
|
|
|
|
|
|
|
|
|
|
|
|
|
|
|
|
|
|
|
|
|
|
|
|
|
|
|
|
|
|
|
|
|
|
|