


Product Monograph - Gentamicin Injection USP (Sandoz Canada)
RECENT MAJOR LABEL CHANGES
None at time of most recent authorization.
TABLE OF CONTENTS
Certain sections or subsections that are not applicable at the time of the preparation of the most recent authorized product monograph are not listed.
RECENT MAJOR LABEL CHANGES ............................................................................................. 2
TABLE OF CONTENTS ............................................................................................................... 2
PART I: HEALTHCARE PROFESSIONAL INFORMATION .............................................................. 4
- 1. INDICATIONS ................................................................................................................ 4
1.1. Pediatrics ........................................................................................................................... 5
1.2. Geriatrics ........................................................................................................................... 5
- 2. CONTRAINDICATIONS .................................................................................................. 5
- 3. SERIOUS WARNINGS AND PRECAUTIONS BOX ............................................................. 5
- 4. DOSAGE AND ADMINISTRATION .................................................................................. 6
4.1. Dosing Considerations ....................................................................................................... 6
4.2. Recommended Dose and Dosage Adjustment .................................................................. 7
4.4. Administration .................................................................................................................. 9
- 5. OVERDOSAGE ............................................................................................................. 10
- 6. DOSAGE FORMS, STRENGTHS, COMPOSITION AND PACKAGING ................................ 10
- 7. WARNINGS AND PRECAUTIONS ................................................................................. 11
7.1. Special Populations ......................................................................................................... 15
7.1.1. Pregnancy ........................................................................................................................ 15
7.1.2. Breastfeeding .................................................................................................................. 15
7.1.3. Pediatrics (≤ 12 years of age) .......................................................................................... 15
7.1.4. Geriatrics (> 65 years of age) ........................................................................................... 16
- 8. ADVERSE REACTIONS ................................................................................................. 16
8.1. Adverse Reaction Overview ............................................................................................ 16
8.2. Post-Market Adverse Reactions ...................................................................................... 16
- 9. DRUG INTERACTIONS ................................................................................................. 17
9.1. Serious Drug Interactions ................................................................................................ 17
9.2. Drug Interactions Overview ............................................................................................. 18
9.3. Drug-Drug Interactions .................................................................................................... 18
9.4. Drug-Food Interactions ................................................................................................... 21
9.5. Drug-Herb Interactions .................................................................................................... 21
9.6. Drug-Laboratory Test Interactions .................................................................................. 21
9.7. Drug-Lifestyle Interactions .............................................................................................. 21
9.8. Drug-Vaccine Interactions ............................................................................................... 21
- 10. CLINICAL PHARMACOLOGY ........................................................................................ 21
10.1. Mechanism of Action ...................................................................................................... 21
10.2. Pharmacodynamics ......................................................................................................... 22
10.3. Pharmacokinetics ............................................................................................................ 22
- 11. STORAGE, STABILITY AND DISPOSAL .......................................................................... 24
- 12. SPECIAL HANDLING INSTRUCTIONS ............................................................................ 24
PART II: SCIENTIFIC INFORMATION ........................................................................................ 25
- 13. PHARMACEUTICAL INFORMATION ............................................................................. 25
- 14. CLINICAL TRIALS ......................................................................................................... 26
- 15. MICROBIOLOGY ......................................................................................................... 26
- 16. NON-CLINICAL TOXICOLOGY ...................................................................................... 28
- 17. SUPPORTING PRODUCT MONOGRAPHS ..................................................................... 33
PATIENT MEDICATION INFORMATION ................................................................................... 34
PART I: HEALTHCARE PROFESSIONAL INFORMATION
1. INDICATIONS
Gentamicin Injection USP (gentamicin sulfate) is clinically effective in serious infections caused by susceptible strains of the following bacteria: Pseudomonas aeruginosa, Proteus species (indole negative and indole positive), Escherichia coli, Klebsiella pneumoniae, Enterobacter aerogenes, Serratia marcescens, and Staphylococcus species (methicillin-susceptible strains only).
Gentamicin Injection USP (gentamicin sulfate) may be considered for the treatment of
Staphylococcus infections when other less potentially toxic drugs are contraindicated and bacterial susceptibility tests and clinical judgment indicate its use.
The use of gentamicin is indicated in the treatment of serious infections caused by laboratory determined susceptible bacteria, with due regard for relative antibiotic toxicity. Therefore, the drug should be considered for treatment of:
- Bacteremia
- Respiratory tract infections
- Urinary tract infections
- Infected wounds: surgical and traumatic
- Bone and soft tissue infections, including peritonitis and burns complicated by sepsis
In the majority of cases bacteriologic cultures should be obtained initially to identify the causative organism(s) and to determine susceptibility to gentamicin. Sensitivity discs of 2 mcg and 10 mcg are available for this purpose.
In suspected or documented gram-negative septicemia, particularly when shock or hypotension is present, gentamicin should be considered for initial antimicrobial therapy.
If anaerobic organisms are suspected, additional antimicrobial therapy should be added to the gentamicin regimen.
The decision to continue therapy with gentamicin should be based on results of the antimicrobial susceptibility tests, clinical response of the patient, and consideration of relative antibiotic toxicity.
Clinical studies have shown that organisms previously sensitive to gentamicin have become resistant during therapy. Acquired resistance to one aminoglycoside does not necessarily confer resistance to other agents in the class.
If susceptibility tests indicate the causative organism is resistant to gentamicin, other tests or additional antimicrobial therapy should be instituted.
Combined therapy with gentamicin and a penicillin type of drug has been used in suspected sepsis until bacteriological studies have identified the etiological organism.
1.1. Pediatrics
Pediatrics (≤ 12 years): Based on the data submitted and reviewed by Health Canada, the safety and efficacy of Gentamicin Injection USP in pediatric patients has been established.
Therefore, Health Canada has authorized an indication for pediatric use.
Gentamicin Injection USP (gentamicin sulfate) should not be used in newborns, infants and neonates except for the treatment of life-threatening infections. Dose adjustments for children are necessary (see 7. WARNINGS AND PRECAUTIONS and 4. DOSAGE AND
ADMINISTRATION).
1.2. Geriatrics
Geriatrics (> 65 years of age): Dose adjustment may be required for elderly patients due to age related decline in glomerular filtration rate. Gentamicin Injection USP should be used with caution in patients with auditory, vestibular or neuromuscular dysfunction (see 7. WARNINGS AND PRECAUTIONS and 4. DOSAGE AND ADMINISTRATION).
To reduce the development of drug-resistant bacteria and maintain the effectiveness of Gentamicin Injection USP and other antibacterial drugs, Gentamicin Injection USP should be used only to treat infections that are proven or strongly suspected to be caused by susceptible bacteria. When culture and susceptibility information are available, they should be considered in selecting or modifying antimicrobial therapy. In the absence of such data, local epidemiology and susceptibility patterns may contribute to the empiric selection of therapy.
2. CONTRAINDICATIONS
The use of Gentamicin Injection USP (gentamicin sulfate) is contraindicated in patients with:
- A history of hypersensitivity or serious toxic reactions to gentamicin or to other aminoglycosides because of the known cross-sensitivity of patients to drugs in this class.
A history of hypersensitivity to gentamicin or any ingredient in the formulation or
component of the container. For a complete listing, see the 6. DOSAGE FORMS,
STRENGTHS, COMPOSITION AND PACKAGING section of the product monograph.
- SERIOUS WARNINGS AND PRECAUTIONS BOX
Serious Warnings and Precautions
- Gentamicin is potentially nephrotoxic, therefore renal function should be assessed prior to and regularly during treatment. Adequate therapeutic peak and trough serum concentrations of gentamicin should be maintained and higher potentially toxic levels should be avoided during therapy. Dosage adjustment is required in children and in patients with renal dysfunction (See 7. WARNINGS AND PRECAUTIONS, Renal, Special Populations, Pediatric (≤ 12 years of age) and Geriatrics (≥ 65 years of age); Monitoring and Laboratory Tests, Renal; 8. ADVERSE REACTIONS; 4. DOSAGE AND ADMINISTRATION; 10. CLINICAL PHARMACOLOGY).
- Gentamicin is potentially ototoxic (vestibular and auditory), therefore patients receiving Gentamicin Injection USP should be closely monitored for eighth cranial nerve toxicity. The ototoxicity is usually associated with high serum levels and renal insufficiency (See 7. WARNINGS AND PRECAUTIONS, Ear/Nose/Throat; Monitoring and Laboratory Tests, Audiological Assessment; 8. ADVERSE REACTIONS).
- The prior/concurrent and/or sequential system or topical use of other potentially nephrotoxic/neurotoxic drugs should be avoided with Gentamicin Injection USP treatment (See 7. WARNINGS AND PRECAUTIONS, Ear/Nose/Throat, and Renal; 9. DRUG INTERACTIONS, Drug-Drug Interactions).
4. DOSAGE AND ADMINISTRATION
4.1. Dosing Considerations
Gentamicin Injection USP is usually given intramuscularly. The intravenous route generally is reserved for circumstances when the intramuscular route is not feasible or advisable (e.g.
shock, hemorrhagic disorders, extensive burns, reduced muscle mass, renal impairment, large injection volumes).
Using the recommended doses, considerable variation in the serum concentration between individual patients has been observed. Monitoring of peak and trough gentamicin serum concentrations is important to insure adequate therapeutic concentration which may be critical, while at the same time avoiding potentially toxic concentrations. Following intravenous or intramuscular administration, 2 or 3 times daily, the peak concentration, measured 30 minutes to 1 hour after administration, is expected to be in the range of 4 to 6 mcg/mL. With once daily administration, transient, high peak concentrations can be anticipated. With all regimens, the dosages should be adjusted to avoid prolonged concentrations above 10 to 12 mcg/mL. Trough levels above 2 mcg/mL, measured just before the next dose, should also be avoided. Determination of the adequacy of a serum level for a particular patient must take into consideration susceptibility of the causative microorganism, severity of infection, and the status of the patient’s host-defence mechanisms.
The patient’s pre-treatment body weight should be obtained for calculation of correct dosage.
For obese patients, the dosage calculation should be based on an estimate of lean body mass.
The usual duration of treatment for all patients is 7 to 10 days. In complicated infections, a longer course of therapy may be necessary. In such cases, monitoring of renal, auditory and vestibular functions is recommended, since toxicity is more likely to occur with treatment extended over 10 days. Dosage should be reduced if clinically indicated.
4.2. Recommended Dose and Dosage Adjustment
INTRAMUSCULAR INJECTION - Patients with Normal Renal Function
Urinary Tract Infections: Gentamicin is highly concentrated in urine and renal tissue. In patients with lower urinary tract infection, particularly if chronic or recurrent and without evidence of impairment of renal function, Gentamicin Injection USP may be administered intramuscularly either in a dose of 160 mg once a day or 80 mg twice a day for 7 to 10 days. For adults weighing less than 60 kg, the single daily dose should be 3 mg/kg of body weight.
Upper urinary tract infections, such as pyelonephritis, and more particularly if there are signs of systemic involvement, should be treated according to one of the dosage schedules for systemic infections.
Since gentamicin activity is increased at pH 7.5, it may be advantageous to alkalinize the urine of patients for urinary tract infections.
Systemic Infections:
Adults: The recommended dosage of Gentamicin Injection USP for adult patients with serious infections and normal renal function is 3 mg/kg/day administered intramuscularly in three equal doses. Therefore, for patients weighing over 60 kg, the usual dosage is 80 mg three times daily. For patients weighing 60 kg or less, the usual dosage is 60 mg three times a day.
The usual duration of treatment is 7 to 10 days. In difficult and complicated infections, a longer course of therapy may be necessary. In such cases, monitoring of renal, auditory and vestibular functions is advisable.
Life-Threatening Infections: In patients with life-threatening infections, dosages up to 5 mg/kg/day should be administered in three or four equally divided doses. This dosage should be reduced to 3 mg/kg/day as soon as clinically indicated.
Special Populations
Pediatrics (≤ 12 years of age)
The precautions for the treatment of infection in children are the same as those for adults.
In severe infections, the recommended dosage is 6-7.5 mg/kg/day (2 to 2.5 mg/kg administered every eight (8) hours).
Infants and Neonates (˃1 week of age)
In infants and neonates older than 1 week, a Gentamicin Injection USP dosage of 7.5 mg/kg/day (2.5 mg/kg administered every 8 hours) is recommended. Using these recommended doses, considerable variation in the serum levels between individual children has been observed therefore monitor serum levels regularly. A serum level in excess of 10-12 mcg/mL following intramuscular administration should be considered potentially toxic.
Pre-term or Full-Term Newborns (≤1 week of age)
In pre-term and full-term newborns, one week of age or less, a dosage of 5 mg/kg/day (2.5 mg/kg administered every 12 hours) is recommended. Use Gentamicin Injection USP with caution in pre-term newborns (post conceptional age of ≤ 38 weeks) because of their renal immaturity.
The above dosage schedules are not intended as rigid recommendations but are provided as guides to dosage. A variety of methods (e.g., microbiologic, enzymatic and radioimmunoassay techniques) are available to measure gentamicin concentrations in body fluids.
The usual duration of treatment is 7 to 10 days. In difficult and complicated infections, a longer course of therapy may be necessary. In such cases monitoring of renal, auditory and vestibular functions is advisable since they are at greater risk of gentamicin-related toxicities (See
Monitoring and Laboratory Tests).
Patients with Impaired Renal Function
Dosage must be adjusted in patients with impaired renal function (Table 1). Since the creatinine clearance rate and serum creatinine concentration have high correlation with the serum half-life of gentamicin, these laboratory tests may provide the guidance necessary for adjustment of the interval between doses of gentamicin. The serum half-life (in hours) of gentamicin may be estimated by multiplying the serum creatinine (mg/100 mL) by four. The frequency of administration (in hours) may be approximated by doubling the serum half-life.
Table 1: Approximate Dosage Guidelines for Gentamicin In Adult Patients Based On Renal Function
| Body Weight Adult Patient | Dose | RENAL FUNCTION TESTS | |||||||||
|---|---|---|---|---|---|---|---|---|---|---|---|
Creatinine Clearance Rate (mL/min) | Serum Creatinine (mg %) | Blood Urea Nitrogen (mg %) | Frequency of Administration | ||||||||
Over 60 kg (132 lb) | 80 mg (2 mL) | Over 70 | Less than 1.4 | Less than 18 | Every 8 hours | ||||||
| 35 – 70 | 1.4 – 1.9 | 18 – 29 | Every 12 hours | ||||||||
| 24 – 34 | 2.0 – 2.8 | 30 – 39 | Every 18 hours | ||||||||
| 16 – 32 | 2.9 – 3.7 | 40 – 49 | Every 24 hours | ||||||||
| 10 – 15 | 3.8 – 5.3 | 50 – 74 | Every 36 hours | ||||||||
| 5 – 9 | 5.4 – 7.2 | 75 – 100 | Every 48 hours | ||||||||
60 kg or less (132 lb) | 60 mg (1.5 mL) | Same as above | |||||||||
In patients with renal failure who are undergoing 14-hour hemodialysis twice weekly, administration of gentamicin, 1 mg/kg, at the end of each dialysis period has been suggested.
In those instances when only a blood urea nitrogen (BUN) concentration is available, this value may be utilized initially, however, it should be supplemented with a serum creatinine level or creatinine clearance rate whenever possible.
This dosage schedule is not intended as a rigid recommendation but is provided as a guide in dosage when the measurement of gentamicin serum levels is not feasible. It should be used in conjunction with close clinical and laboratory observations of the patients and modified as deemed necessary by the treating physician.
INTRAVENOUS INJECTION
The recommended dosage for intravenous administration is 3 mg/kg/day in three equally divided doses, identical to that recommended for intramuscular use.
4.4. Administration
Gentamicin Injection USP may be given IM or IV. Gentamicin Injection USP is usually given as an intramuscular injection. The intravenous route generally is reserved for special indications
(see 4.1. Dosing Considerations).
Compatibility
Gentamicin Injection USP should not be physically premixed with other drugs, but should be administered separately in accordance with the recommended route of administration and dosage schedule.
For intravenous administration Gentamicin Injection USP may be added to 0.9% sodium chloride injection or 5% dextrose injection. Gentamicin Injection USP is compatible and stable for 24 hours when diluted to 0.35-0.7 mg/mL with either 0.9% sodium chloride injection or 5% dextrose injection. The diluted infusion mixture should be prepared immediately before use and any portion not used within 24 hours must be discarded.
As with all parenteral drug products, intravenous admixtures should be inspected visually for clarity, particulate matter, precipitation, discolouration and leakage prior to administration whenever solution and container permit. Solutions showing haziness, particulate matter, precipitate, discolouration or leakage should not be used. Discard unused portion.
Dilution and Infusion:
For intravenous administration, a single dose (1 mg/kg) of Gentamicin Injection USP must be diluted in 100-200 mL of 0.9% sodium chloride injection or 5% dextrose injection. The solution is infused over a period of one to two hours and repeated every eight hours, if necessary.
A single dose of Gentamicin Injection USP undiluted may also be given directly into the side-arm of intravenous tubing set, slowly over a period of two to three minutes and repeated every eight hours, if necessary.
5. OVERDOSAGE
In the event of overdose or toxic reactions, peritoneal dialysis or hemodialysis will aid in the removal of gentamicin from the blood. These procedures are of particular importance in patients with impaired renal function.
For the most recent information in the management of a suspected drug overdose, contact your regional poison control centre or Health Canada’s toll-free number, 1-844 POISON-X (1-844-764-7669).
6. DOSAGE FORMS, STRENGTHS, COMPOSITION AND PACKAGING
Table 2 – Dosage Forms, Strengths, and Composition
| Route of Administration | Dosage Form / Strength / Composition | Non-Medicinal Ingredients |
|---|---|---|
Intramuscular injection Intravenous infusion | aqueous solution 10 mg/mL or 40 mg/mL gentamicin | Methylparaben (40 mg/mL strength only), propylparaben (40 mg/mL strength only), disodium edetate dihydrate, sodium hydroxide, sodium bisulfite, sulfuric acid, and water for injection |
Description
Gentamicin Injection USP is a sterile, nonpyrogenic, aqueous solution for parenteral administration.
Gentamicin Injection USP, 10 mg/mL, is available in 2 mL single use vials, boxes of 10. Discard unused portion.
Gentamicin Injection USP, 40 mg/mL, is available in 2 mL and 20 mL multidose vials, boxes of 10 and 1, respectively. Discard 28 days after initial use.
Each mL of the 10 mg/mL product contains: Gentamicin sulfate equivalent to gentamicin 10 mg; sodium bisulfite 1.625 mg as antioxidant; disodium edetate dihydrate 0.1 mg; sodium hydroxide and/or sulfuric acid for pH adjustment, and water for injection.
Each mL of the 40mg/mL product contains: Gentamicin sulfate equivalent to gentamicin 40 mg; methylparaben 1.8 mg and propylparaben 0.2 mg as preservatives; sodium bisulfite 3.2 mg as antioxidant; disodium edetate dihydrate 0.1 mg; sodium hydroxide and/or sulfuric acid for pH adjustment, and water for injection.
7. WARNINGS AND PRECAUTIONS
Please see 3. SERIOUS WARNINGS AND PRECAUTIONS BOX.
General
Patients treated with aminoglycosides should be under close clinical observation because of the potential toxicity associated with their use.
Prescribing Gentamicin Injection USP in the absence of a proven or strongly suspected bacterial infection is unlikely to provide benefit to the patient and risks the development of drug-resistant bacteria.
As with other antibiotics, treatment with gentamicin may result in overgrowth of non- susceptible organisms resulting in superinfection. If superinfection occurs, appropriate measures should be taken.
Ear/Nose/Throat
Ototoxicity has been reported with the use gentamicin, as with the antibiotics streptomycin, neomycin and kanamycin. This adverse reaction, which may be delayed in onset, is manifested primarily by damage to vestibular function. The reversibility of this adverse reaction is frequently contingent upon early recognition of potential ototoxicity.
Complete damage has occurred mainly in patients who were uremic, had renal dysfunction, had prior therapy with ototoxic drugs or received higher doses and longer courses of therapy than those recommended.
In patients who have previously been treated with drugs likely to affect eighth cranial nerve function (e.g., streptomycin, neomycin, kanamycin, etc.) Gentamicin Injection USP should be used with caution and with the understanding that toxic effects may be cumulative with these agents.
To reduce the risk of ototoxicity, if a patient reports tinnitus or hearing loss during therapy, the physician should refer them for audiological assessment. If ototoxicity occurs in a patient receiving Gentamicin Injection USP, stop the drug and substitute treatment with an alternative nonototoxic agent. If discontinuation is not possible, then the dosage should be adjusted so that trough serum concentration falls below 2 mcg/mL.
Potent diuretics such as ethacrynic acid and furosemide have been associated with eighth cranial nerve dysfunction, and the concomitant use of either of these drugs with gentamicin should be avoided. It is believed that intravenous diuretics may cause fairly rapid rise in gentamicin serum levels and potentiate ototoxicity.
In patients with impaired renal function, the frequency of gentamicin administration should be reduced, and renal function should be monitored along with evaluation of auditory and vestibular function. Serum concentrations of gentamicin should be monitored whenever feasible; prolonged concentrations above 12 mcg/mL should be avoided (see 4. DOSAGE AND ADMINISTRATION).
Gastrointestinal
Clostridium difficile-associated disease (CDAD) has been reported with use of many antibacterial agents, including gentamicin. CDAD may range in severity from mild diarrhea to fatal colitis. It is important to consider this diagnosis in patients who present with diarrhea or symptoms of colitis, pseudomembranous colitis, toxic megacolon, or perforation of the colon subsequent to the administration of any antibacterial agent. CDAD has been reported to occur over 2 months after the administration of antibacterial agents.
Treatment with antibacterial agents may alter the normal flora of the colon and may permit overgrowth of Clostridium difficile. Clostridium difficile produces toxins A and B, which contribute to the development of CDAD. CDAD may cause significant morbidity and mortality.
CDAD can be refractory to antimicrobial therapy.
If the diagnosis of CDAD is suspected or confirmed, appropriate therapeutic measures should be initiated. Mild cases of CDAD usually respond to discontinuation of antibacterial agents not directed against Clostridium difficile. In moderate to severe cases, consideration should be given to management with fluids and electrolytes, protein supplementation, and treatment with an antibacterial agent clinically effective against Clostridium difficile. Surgical evaluation should be instituted as clinically indicated since surgical intervention may be required in certain severe cases (see 8. ADVERSE REACTIONS).
Immune
Hypersensitivity: Serious and occasionally fatal hypersensitivity (anaphylactic) reactions have been reported in patients receiving gentamicin. Gentamicin Injection USP is contraindicated in patients with a known history of hypersensitivity (allergic) reaction to any aminoglycoside.
Gentamicin Injection USP should be discontinued if a hypersensitivity reaction to Gentamicin
Injection USP occurs and appropriate therapy should be instituted (see 8. Adverse Reactions).
Monitoring and Laboratory Tests
Gentamicin has demonstrated the listed laboratory test abnormalities. While clinical laboratory test abnormalities may be isolated findings, they may be associated with clinically related signs and symptoms (See 8. ADVERSE REACTIONS). For example, tetany and muscle weakness may be associated with hypomagnesaemia, hypocalcaemia, and hypokalemia.
The following tests should be conducted at the discretion of the treating physician.
Renal
Assess laboratory tests of urine and renal function prior to and regularly during treatment.
Serum Drug Levels
Monitor peak and trough gentamicin serum concentrations during Gentamicin Injection USP therapy to assure adequate serum levels and to avoid potentially toxic levels. Avoid peak serum concentrations above 12 mcg/mL and trough concentrations above 2 mcg/mL. If concentrations exceed these levels, discontinue gentamicin therapy or adjust the dosage so that the trough gentamicin serum concentration falls below 2 mcg/mL.
Electrolytes
Monitor electrolytes in patients receiving Gentamicin Injection USP.
Audiological Assessment
For patients with known or suspected auditory or vestibular dysfunction and those who are at increased risk for vestibular or auditory dysfunction, audiological assessment should be considered before initiating Gentamicin Injection USP therapy. If a patient reports tinnitus or hearing loss during or following Gentamicin Injection USP therapy, refer the patient for audiological assessment.
Neurologic
Neurological adverse reactions (vertigo, gait ataxia, dizziness, numbness, skin tingling, muscle twitching, convulsions, seizure) including serious adverse drug reactions, (e.g., peripheral motor and/or sensory polyneuropathy, encephalopathy) have been reported following administration of Gentamicin for injection to patients. If a neurotoxic reaction occurs, discontinue use of Gentamicin Injection USP immediately.
During or following Gentamicin for injection therapy, paresthesia, tetany, positive Chvostek and Trousseau signs and mental confusion have been reported in patients with
hypomagnesemia, hypocalcemia and hypokalemia. When this has occurred in infants, tetany and muscle weakness has been reported. Electrolytes should be monitored in patients receiving Gentamicin Injection USP. If paresthesia and positive Chvostek and Trousseau signs do occur, corrective electrolyte therapy should be initiated both in adults and infant patients
(See Monitoring and Laboratory Tests, Electrolytes; 8. ADVERSE REACTIONS).
Neuromuscular Blocking Action: Caution should be exercised when Gentamicin Injection USP is prescribed to patients with known or suspected neuromuscular disorders such as myasthenia gravis or Parkinson’s disease. If signs of respiratory paralysis do occur, discontinue administration of Gentamicin Injection USP immediately. Provide supportive care as clinically indicated.
Aminoglycosides, including Gentamicin Injection USP, may aggravate muscle weakness because of their potential curare-like effects on the neuromuscular junction. Neuromuscular blockade (flaccid paralysis, dilated pupils and weakness of the respiratory musculature), is generally dose dependent and self-limiting. Neuromuscular blockade and myasthenia gravis- like syndrome have been reported with gentamicin for injection therapy. Recovery from gentamicin-induced neuromuscular blockade may be slow, and prolonged blockade has been described with chronic administration. Neuromuscular blockage and respiratory paralysis have been reported in cats receiving high doses (40 mg/kg) of gentamicin sulfate (See 8. ADVERSE
REACTIONS, 8.5 Post-Market Adverse Drug Reactions).
Rapid injection of aminoglycoside antibiotics including gentamicin can cause neuromuscular blockade therefore, when administering Gentamicin Injection USP intravenously, infuse over at least 30 minutes.
Avoid concurrent use of neuromuscular blocking curariform muscle relaxants and other potential neurotoxic agents which may precipitate respiratory depression. The possibility of neuromuscular blockade and respiratory paralysis should be considered if Gentamicin Injection
USP is administered to patients receiving muscle relaxants or paralytic agents, which are commonly used in patients undergoing anesthesia. Patients receiving massive transfusions of citrate anticoagulated blood may also experience weakness caused by a decreased free calcium concentration. In both adults and infants, if neuromuscular blockade occurs, calcium salts or neostigmine should be administered to counteract gentamicin associated neuromuscular blockade. (See 8. ADVERSE REACTIONS, 8.5 Post-Market Adverse Drug Reactions; 9. DRUG INTERACTIONS, Drug-Drug Interactions).
Ophthalmologic
Serious adverse reactions (reduced visual acuity, oscillopsia and partial loss of eyesight) have been reported with gentamicin. If signs of visual disorders appear, discontinue Gentamicin
Injection USP treatment or adjust dosage (See 8. ADVERSE REACTIONS).
Peri-Operative Considerations
Aminoglycosides may produce neuromuscular blockade when used in combination with neuromuscular blocking agents.
Renal
Acute renal failure, tubular necrosis, toxic nephropathy and interstitial nephritis with hospitalization and dialysis have been reported with gentamicin. Acute renal failure including fatality has been reported in a patient receiving inadvertent gentamicin outside the recommended dose.
Caution should be exercised when administering Gentamicin Injection USP to patients with known or suspected renal dysfunction, to patients that develop signs of nephrotoxicity, to patients with higher gentamicin serum concentrations, dehydration, hypovolemia, shock and liver disease, to patients concomitantly or sequentially administrated other potentially nephrotoxic agents and also to children (including neonates, pre-term/full-term newborns), elderly and females.
Adjust Gentamicin Injection USP dosage to ensure therapeutically adequate, but not potentially toxic and excessive, drug levels in blood. Avoid peak serum concentrations above
12 mcg/mL and trough concentrations above 2 mcg/mL during therapy.
Acute renal injury is usually reversible following discontinuation of the aminoglycoside, but can also lead to severe uremia and possibly death. On rare occasions, changes in renal function may not manifest until soon after completion of therapy.
Assess baseline renal function and monitor laboratory tests of urine and renal function regularly because patients receiving high dose or treatment for longer duration have demonstrated increased risk of nephrotoxicity (See 8. ADVERSE REACTIONS). If nephrotoxicity occurs in a patient receiving Gentamicin Injection USP, stop the drug and substitute treatment with an alternative non-nephrotoxic agent. If discontinuation is not possible, then adjust dosage so that trough serum concentration falls below 2 mcg/mL.
7.1. Special Populations
7.1.1. Pregnancy
Gentamicin Injection USP is not recommended during pregnancy except in life-threatening situations where the potential benefits outweigh the potential risk to the fetus.
Aminoglycosides, like gentamicin, cross the placenta and may be found in fetal serum and amniotic fluid resulting in fetal harm when administered to pregnant woman. There have been reports of total irreversible bilateral congenital deafness in children whose mothers received aminoglycosides, including gentamicin, during pregnancy.
If Gentamicin Injection USP is used during pregnancy or if the patient becomes pregnant while taking Gentamicin Injection USP, the patient should be apprised of the potential hazard to the fetus.
7.1.2. Breastfeeding
The safety and efficacy of gentamicin in nursing women have not been established.
Gentamicin is excreted in human breast milk, and nursing infants may have detectable gentamicin levels.
Due to the potential for serious adverse drug reactions in infants receiving gentamicin- containing breast milk, a decision should be made to either discontinue nursing or discontinue the use of Gentamicin Injection USP, taking into account the importance of gentamicin treatment to the mother.
7.1.3. Pediatrics (≤ 12 years of age)
Gentamicin Injection USP should not be used in the newborns, neonates and infants except for the treatment of life-threatening infections. Higher serum levels and prolonged half-life of gentamicin has been reported in children (including infants, neonates, and pre-term/full-term newborns).
Gentamicin Injection USP may not be appropriate for use in children. Dosage adjustments are required in children. Use Gentamicin Injection USP with caution and assess serum concentration and renal function regularly during treatment.
7.1.4. Geriatrics (> 65 years of age)
The elimination of gentamicin may be prolonged in geriatric patients, due to the age-related decline in glomerular filtration rate. Renal function should be assessed prior to and regularly during gentamicin therapy. The dosage regimen should be adjusted according to renal function. Gentamicin serum levels may require monitoring. Risk factors for gentamicin toxicity occur more frequently in the geriatric population.
8. ADVERSE REACTIONS
8.1. Adverse Reaction Overview
The most frequently reported serious adverse drug reactions associated with gentamicin includes nephrotoxicity (including acute renal failure, renal tubular necrosis, toxic nephropathy) and ototoxicity (including irreversible hearing loss).
Gentamicin may cause specific damage to the lining cells of renal proximal tubules. The incidence of reported nephrotoxic damage in aminoglycoside-treated patients ranges from 5 to almost 40% depending on the type of patients studied, the definition of nephrotoxicity, and intensity of renal monitoring.
8.2. Post-Market Adverse Reactions
Since clinical studies are not available for Gentamicin Injection USP, all adverse drug reactions are presented in the post-market adverse drug reactions section.
Adverse reactions reported and possibly related to gentamicin are summarized in Table 3:
Table 3: Adverse Reactions Reported and Possibly Related to Gentamicin
| Blood and Lymphatic System | Increased reticulocyte counts; decreased reticulocyte counts; anaemia; haemolytic anemia; pancytopenia; granulocytopenia; thrombocytopenia; leukopenia; eosinophilia; transient agranulocytosis; decreased hemoglobin and hematocrit; purpura, splenomegaly; haemolysis; febrile neutropenia; haemolysis. |
|---|---|
| Cardiac | Tachycardia |
| Ear and Labyrinth | Vertigo; vestibular disorder; tinnitus; deafness; ototoxicity; and impaired hearing. |
| Ophthalmologic | Blurred vision; visual disturbances; vision impairment; diplopia; oscillopsia. |
| Gastrointestinal | Vomiting; nausea; decreased appetite; increased salivation; weight loss; gastrointestinal hemorrhage; laryngeal edema and spasm; stomatitis. |
General Disorders and Administration Site Conditions | Gait disturbance; fatigue; pyrexia; feeling abnormal; generalized burning; local swelling; abasia. |
| Hepatic | Increased serum transaminase (AST, ALT); increased serum bilirubin; transient hepatomegaly. |
| Immune System | Drug fever, anaphylactoid reactions; anaphylactic reaction. |
| Infections and Infestations | Bacteraemia; citrobacter infection; gastroenteritis viral; pathogen resistance; sepsis neonatal. |
Injury, Poisoning and Procedural Complications | Fall; pain at the injection site; toxicity to various agents; maternal exposure during pregnancy; foetal exposure during pregnancy; 8th nerve injury. |
| Investigations | Blood calcium increased; decrease in serum calcium, magnesium, sodium and potassium; increased blood pressure; increased serum LDH |
Metabolism and nutrition disorders | hypervolemia |
Musculoskeletal and Connective Tissue | Back pain; joint pain; alopecia and muscle twitching. |
| Nervous System | Lethargy; skin tingling; numbness; headache; confusion; dizziness; balance disorder; speech disorder; cognitive disorder; tremor; memory impairment; fifth nerve paresthesia; convulsions; pseudotumor cerebri; acute organic brain syndrome; speech disorder developmental; hydrocephalus; neuromuscular blockade. |
| Psychiatric | Disorientation; insomnia; depression; abnormal thinking. |
| Renal and Urinary | Renal failure, acute renal failure; tubulointerstitial nephritis; nephropathy toxic; increased blood creatinine; haemodialysis; renal tubular necrosis; renal impairment; renal pain. |
Respiratory, thoracic and mediastinal disorders | Respiratory depression; pulmonary fibrosis. |
Skin and Subcutaneous Tissue | Rash; itching; rash erythematous; urticaria; subcutaneous atrophy or fat necrosis; Red man syndrome. |
Surgical and Medical Procedures | Haemodialysis. |
| Vascular disorders | hypotension; hypertension |
9. DRUG INTERACTIONS
9.1. Serious Drug Interactions
Concurrent or sequential use of other neurotoxic, ototoxic and/or nephrotoxic drugs can increase the possibility of gentamicin toxicity.
Co-administration of Gentamicin Injection USP with neuromuscular blocking agents should be avoided (See 9. DRUG INTERACTIONS, Drug-Drug Interactions).
9.2. Drug Interactions Overview
Gentamicin Injection USP should not be administered concurrently/subsequently with the following drugs with nephrotoxic, ototoxic or neurotoxic potential. Neuromuscular blockade and respiratory paralysis have been reported in cats receiving high doses (40 mg/kg) of gentamicin. The possibility of this phenomenon in man should be considered if aminoglycosides, including Gentamicin Injection USP, are administered by any route to patients receiving anesthetics or neuromuscular blocking agents or massive transfusions of citrate-anticoagulated blood.
9.3. Drug-Drug Interactions
The drugs listed in this table are based on either drug interaction case reports or studies, or potential interactions due to the expected magnitude and seriousness of the interaction (i.e., those identified as contraindicated).
Table 4 - Established or Potential Drug-Drug Interactions
| [Proper/Common name] | Source of evidence | Effect | Clinical comment |
|---|---|---|---|
| [Proper/Common name] | Source of evidence | Effect | Clinical comment |
| [Proper/Common name] | Source of evidence | Effect | Clinical comment |
Antimicrobials Aminoglycosides (e.g., Amikacin, Kanamycin, Parmomycin, Streptomycin, Tobramycin) Amphotericin B Cephalosporins (e.g., cephaloridine, cephalothin) Clindamycin Polymyxin B, Polymyxin E (colistin) Vancomycin | L | Increased risk of nephrotoxicity and/or neurotoxicity/ ototoxicity. | Avoid concomitant and/or sequential use. Monitor laboratory tests of urine and renal function. If nephrotoxicity occurs, stop the drug and substitute treatment with an alternative non- nephrotoxic agent. If discontinuation is not possible, then adjust dosage so that trough serum concentration falls below 2 mcg/mL. Conduct/refer for audiological assessment. |
Carbenicillin, Piperacillin | L | A reduction in gentamicin serum half-life has been reported in patients with severe renal impairment receiving carbenicillin and piperacillin | Avoid concomitant and/or sequential use. |
concomitantly with gentamicin for injection. | |||
Cholinergic agents (e.g., neostigmine, pyridostigmine) | L | Gentamicin antagonizes the effect of neostigmine and pyridostigmine. | Avoid concomitant use. |
Loop Diuretics (e.g., Bumetanide, Ethacrynic acid, Furosemide, Piretanide) | L | Increases the risk for ototoxic and nephrotoxic effects of aminoglycosides, including gentamicin. | Concomitant use of Gentamicin Injection USP with potent loop diuretics should be avoided. Monitor laboratory tests of urine and renal function. If renal dysfunction occurs, adjust dosage of Gentamicin Injection USP. Monitor for signs of ototoxicity. |
Neuromuscular blocking agents and opioid-analgesics (e.g., Atracurium, Alfentanyl, Decamethonium, Fentanyl, Succinylcholine, Sufentanil, Trimethaphan, Tubocurarine, Vecuronium) | L | Increased risk of neuromuscular blockade. | Avoid concomitant use. Monitor respiratory function. Provide supportive care if an interaction occurs. |
Anti-neoplastic Agents (e.g., Carboplatin, Cisplatin) | L | Increased risk of nephrotoxicity and/or neurotoxicity | Avoid concomitant and/or sequential use. Monitor laboratory tests of urine and renal function. If nephrotoxicity occurs, stop the drug and substitute treatment with an alternative non- nephrotoxic agent. If discontinuation is not possible, then adjust dosage so that trough serum concentration falls below 2 mcg/mL. |
Immunosuppresive Agents (e.g., Cyclosporine, Tacrolimus) | L | Increased risk of nephrotoxicity and/or neurotoxicity | Avoid concomitant and/or sequential use. Monitor laboratory tests of urine and renal function. If nephrotoxicity |
| occurs, stop the drug and substitute treatment with an alternative non- nephrotoxic agent. If discontinuation is not possible, then adjust dosage so that trough serum concentration falls below 2 mcg/mL. | |||
| Zalcitabine | L | Increased risk of nephrotoxicity and/or neurotoxicity | Avoid concomitant and/or sequential use. Monitor laboratory tests of urine and renal function. If nephrotoxicity occurs, stop the drug and substitute treatment with an alternative non- nephrotoxic agent. If discontinuation is not possible, then adjust dosage so that trough serum concentration falls below 2 mcg/mL. |
| Mannitol | L | Increased risk of nephrotoxicity and/or neurotoxicity | Avoid concomitant and/or sequential use. Monitor laboratory tests of urine and renal function. If nephrotoxicity occurs, stop the drug and substitute treatment with an alternative non- nephrotoxic agent. If discontinuation is not possible, then adjust dosage so that trough serum concentration falls below 2 mcg/mL. |
| Agalsidase α and β | L | Inhibition of intracellular α- galactosidase | Avoid concomitant use. |
| Indomethacin | L | Increased gentamicin serum concentrations in infants | Avoid concomitant use. Monitor laboratory tests of urine and renal function. If nephrotoxicity occurs, stop the drug and substitute treatment with an alternative non- nephrotoxic agent. If discontinuation is not possible, then adjust dosage so that trough serum concentration falls below 2 mcg/mL. |
| Magnesium | L | Increased neuromuscular blockade | Avoid concomitant use. Concomitant use may potentiate muscle relaxant effect. |
Legend: L = Literature
9.4. Drug-Food Interactions
Interactions with food have not been established.
9.5. Drug-Herb Interactions
Interactions with herbal products have not been established.
9.6. Drug-Laboratory Test Interactions
Interactions with laboratory tests have not been established.
9.7. Drug-Lifestyle Interactions
Interactions with lifestyle choices have not been established.
9.8. Drug-Vaccine Interactions
Gentamicin Injection USP may interfere with the immunological response of live typhoid vaccine and reduce effectiveness of BCG (Bacillus of Calmette and Guerin) vaccine and should not be concomitantly administered.
Gentamicin Injection USP may have an additive risk of neuromuscular blockade if administered concomitantly with Botulism toxin. Avoid concurrent use. If given together, monitor respiratory function.
10. CLINICAL PHARMACOLOGY
10.1. Mechanism of Action
The antimicrobial action of aminoglycosides is facilitated by their chemical structure. These antibiotics can be considered as polycationic species. Because they are polycationic, they show binding affinity for negatively charged residues in the outer membrane of Gram-negative bacilli and in nucleic acids. Their bactericidal activity is due to inhibition of bacterial protein synthesis through binding to prokaryotic 16S rRNA and disruption of the integrity of the bacterial cell membrane. The uptake process is self-promoted involving the drug-induced disruption of Mg2+ bridges between adjacent lipopolysaccharide molecules. They show their bactericidal activity through a multistep process.
First, aminoglycosides bind electrostatically to negatively charged residues in the outer membrane of Gram-negative bacteria in a passive, nonenergy dependent process. Then they diffuse through outer membrane porin channels and enter the periplasmic space. Their subsequent transport across the cytoplasmic membrane requires metabolic energy from the electron transport system in an oxygen-dependent process. This phase of transport has been termed energy dependent phase I (EDP-I) and is the rate limiting step. The oxidative energy production required for transport explains why aminoglycosides are much less active in an anaerobic environment. EDP-I can also be inhibited by divalent cations, reduced pH, and hyperosmolarity. In the cytosol, aminoglycosides bind to the 30S subunit of ribosomes through an energy dependent process (EDP-II).
The binding does not prevent the formation of the initiation complex of peptide synthesis, it perturbs the elongation of the nascent chain by impairing the proofreading process controlling translational accuracy. The aberrant proteins may be inserted into the cell membrane, leading to altered permeability and further stimulation of aminoglycoside transport.
10.2. Pharmacodynamics
Aminoglycosides are bactericidal, and their rate of bacterial killing increases as the antibiotic concentration is increased, regardless of the inoculum. Bactericidal concentration of gentamicin is usually one to four times the minimum inhibitory concentration. In the neutropenic thigh model, the therapeutic efficacy of aminoglycosides correlates with the peak serum concentration and the area under the concentration versus time curve over time.
10.3. Pharmacokinetics
Absorption:
After intramuscular (IM) administration of gentamicin sulfate, peak serum concentrations usually occur between 30 and 60 minutes and serum levels are measurable for six to eight hours. When gentamicin is administered by intravenous (IV) infusion over a two-hour period, the serum concentrations are similar to those obtained by IM administration.
In patients with normal renal function, peak serum concentrations of gentamicin (mcg/ml) are usually up to four times the single IM dose (mg/kg); for example, a 1 mg/kg injection in adults may be expected to result in a peak serum concentration up to 4 mcg/ml; a 1.5 mg/kg dose may produce levels up to 6 mcg/ml. While some variation is to be expected due to a number of variables such as age, body temperature, surface area and physiologic differences, the individual patient given the same dose tends to have similar levels in repeated determinations.
Gentamicin, administered at 1 mg/kg every eight hours for the usual 7 to 10 day treatment period to patients with normal renal function does not accumulate in the serum.
Gentamicin, like all aminoglycosides, may accumulate in the serum and tissues of patients treated with higher doses and/or for prolonged periods, particularly in the presence of impaired renal function. In adult patients, treatment with Gentamicin Injection USP dosages of
4 mg/kg/day or higher for 7 to 10 days may result in a slight, progressive rise in both peak and trough concentrations. In patients with impaired renal function, gentamicin is cleared from the body more slowly than in patients with normal renal function. The more severe the impairment, the slower the clearance.
Distribution:
Gentamicin binding to protein is low and may vary between 0 and 30%. Since gentamicin is distributed in extra-cellular fluid, peak serum concentrations may be lower than usual in adult patients who have a large volume of this fluid. Serum concentrations of gentamicin in febrile patients may be lower than those in afebrile patients given the same dose. When body temperature returns to normal, serum concentrations of the drug may rise. Febrile and anemic states may be associated with a shorter than usual serum half-life. (Dosage adjustment is usually not necessary.) In severely burned patients, the half-life may be significantly decreased and resulting serum concentrations may be lower than anticipated from the mg/kg dose.
Following parenteral administration, gentamicin can be detected in serum, lymph, tissues, sputum and in pleural, synovial and peritoneal fluids. Concentrations in renal cortex sometimes may be eight times higher than the usual serum levels. Concentrations in bile, in general, have been low and have suggested minimal biliary excretion. Gentamicin crosses the peritoneal as well as the placental membranes. Since aminoglycosides diffuse poorly into the subarachnoid space after parenteral administration, concentrations of gentamicin in cerebrospinal fluid are often low and dependent upon dose, rate of penetration and degree of meningeal inflammation. There is minimal penetration of gentamicin into ocular tissues following IM or IV administration.
Metabolism:
Little, if any, metabolic transformation occurs; the drug is excreted principally by glomerular filtration.
The creatinine clearance rate and the serum creatinine level have a high correlation with the half-life of gentamicin in serum. Results of these tests may serve as guides for adjusting dosage in patients with renal impairment.
Elimination:
The principal route of excretion is via the kidney, almost exclusively by glomerular filtration with some small fraction of tubular reabsorption. The serum half-life is 2-4 hr in patients with normal renal function. With a progressive decrease in glomerular filtration, there is an inverse proportional change in the rate of clearance of gentamicin such that the serum half-life is approximately 48 hr in patients with glomerular filtration rates of <5 ml per min.
After initial administration to patients with normal renal function, generally 70% or more of the gentamicin dose is recoverable in the urine in 24 hours; concentrations in urine above 100 mcg/ml may be achieved. After several days of treatment, the amount of gentamicin excreted in the urine approaches the daily dose administered. As with other aminoglycosides, a small amount of the gentamicin dose may be retained in the tissues, especially in the kidneys.
Minute quantities of aminoglycosides have been detected in the urine weeks after drug administration was discontinued. Renal clearance of gentamicin is similar to that of endogenous creatinine.
In patients with marked impairment of renal function, there is a decrease in the concentration of aminoglycosides in urine and in their penetration into defective renal parenchyma. This decreased drug excretion, together with the potential nephrotoxicity of aminoglycosides, should be considered when treating such patients who have urinary tract infections.
Special Populations and Conditions
Intramuscular Route
Adults: In patients with normal renal function, peak serum concentrations that are bactericidal for susceptible bacteria occur between 30 and 90 minutes after injection, the peak serum level (mcg/mL) being four times the single dose (mg/kg). The mean serum half-life is approximately two hours.
Infants and Neonates: Peak serum concentrations of 2.2 mcg/mL to 8.6 mcg/mL (mean 4.0 mcg/mL) are observed one-half to one hour after 2.5 mg/kg of gentamicin is administered intramuscularly to infants 7 days of age and under.
The mean serum gentamicin half-life is approximately five hours in neonates under 72 hours of age. The half-life may be considerably prolonged in infants weighing less than 1500 grams (3.3 lbs). In low-birth-weight infants, prolonged half-life values may extend through the second week of life. In contrast, values of 3 to 3.5 hours are usually observed in full-term infants who are 7 days of age or older.
Concentrations of gentamicin in serum of infants 2 to 24 months of age following IM doses of 2.1 and 2.5 mg/kg were shown to be in the range of 2.5 to 7.5 mcg/mL.
Intravenous Route
Adults: After a two-hour infusion of a dose of 1 mg/kg to a group of patients, peak gentamicin concentrations were reached at the end of the infusion and averaged 4.5 mcg/mL (range 0.5 to 8 mcg/mL).
Slow intravenous injection at recommended doses gave serum levels of 5 to 9 mcg/mL after 10 minutes.
The mean serum half-life is the same as for the intramuscular route of administration.
Infants and Neonates: Levels in serum and half-life values after intravenous infusion of gentamicin were similar to those after intramuscular administration.
- 11. STORAGE, STABILITY AND DISPOSAL
Gentamicin Injection USP should be stored between 15 - 30°C. Protect from light.
The chlorobutyl rubber stopper is not made with natural rubber latex.
- 12. SPECIAL HANDLING INSTRUCTIONS
Any unused portion of the single use vials should be discarded immediately.
PART II: SCIENTIFIC INFORMATION
- 13. PHARMACEUTICAL INFORMATION
Drug Substance
Proper name: Gentamicin sulfate
Chemical name: 0-3-Deoxy-4-C-methyl-3-(methylamino)-β-L-arabinopyranosyl-
(1→6)-0-[2,6-diamino-2,3,4,6-tetradeoxy-α-D-erythro- hexopyranosyl-(1→4)]-2-deoxy-D-streptamine
Molecular formula and molecular mass: Gentamicin C1: C21H43N5O7 - 477.6 g/mol
Gentamicin C2: C20H41N5O7 - 463.6 g/mol
Gentamicin C1a: C19H39N5O7 - 449.5 g/mol
Structural formula: Gentamicin Injection USP is a mix of the following three substances:
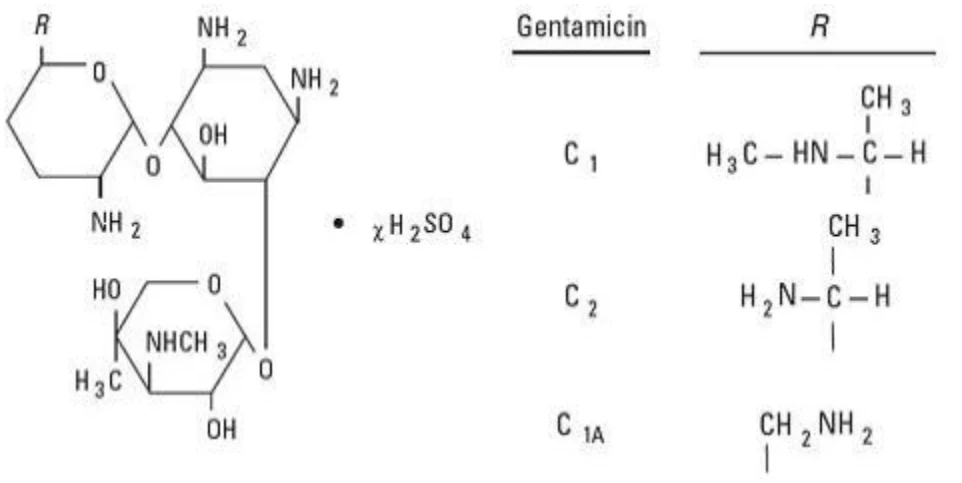
The relative ratio of C1 : C1a : C2 is variable in a range of 25-50 : 10-35 : 25-55%.
Physicochemical properties:
White to buff powder. Soluble in water; insoluble in alcohol, acetone and benzene.
The pH of a 1:25 solution of gentamicin in water is 3.5-5.5.
14. CLINICAL TRIALS
This information is not available.
15. MICROBIOLOGY
Mode of action
Gentamicin is an aminoglycoside antibiotic and has a bactericidal action against many Gram- negative aerobes and against some strains of staphylococci by binding to the 30S, and to some extent to the 50S, subunits of the bacterial ribosome, inhibiting protein synthesis and generating errors in the transcription of the genetic code. The manner in which cell death is brought about is imperfectly understood, and other mechanisms may contribute, including effects on membrane permeability.
Gentamicin is bactericidal in vitro against Gram-positive and Gram-negative bacteria.
Mechanisms of Resistance
Resistance to the aminoglycosides may be acquired by -four main mechanisms:
- 1)
reduction of the intracellular concentration of the antibiotic within bacterial cells,
usually via efflux of the agent out of the bacterial cell by either dedicated or general efflux pumps;
- 2) alteration of the molecular target of the antibiotic, usually as result of a spontaneous mutation in the gene encoding the target or substitution of the target’s function by an exogenous gene;
- 3) enzymatic inactivation of the aminoglycoside;
- 4) presence of plasmid-mediated resistance factor.
Spectrum of Activity
Gentamicin is active against the majority of the following aerobic Gram-positive and Gram negative bacteria both in vitro and in clinical infections:
Aerobic Gram-Positive Bacteria
Staphylococcus aureus (methicillin-susceptible only)
Staphylococcus epidermidis
Aerobic Gram-Negative Bacteria
Escherichia coli
Klebsiella pneumonia
Pseudomonas aeruginosa
Enterobacter aerogenes
Serratia marcescens
Proteus mirabilis
Not all strains of these bacteria are susceptible to gentamicin. In serious or life-threatening infections known or suspected to be caused by these organisms, initial empiric combination therapy should be considered until results of susceptibility tests become available.
The aminoglycosides, including gentamicin, show no inhibitory activity against
Stenotrophomonas maltophilia. All streptococci, including Streptococcus pnuemoniae, and enterococi are resistant to gentamicin. All anaerobic organisms are resistant to this class of drugs.
Susceptibility Test Methods
Dilution Techniques
Quantitative methods are used to determine antimicrobial minimum inhibitory concentrations
(MICs). MICs provide estimates of the susceptibility of bacteria to antimicrobial compounds.
MIC values should be determined using a standardized procedure. Standardized procedures are based on a dilution method (broth or agar) or equivalent with standardized inoculum concentrations and standardized concentrations of gentamicin powder. The MIC values should be interpreted according to the criteria provided in Table 5.
Diffusion Techniques
Quantitative methods that require measurement of zone diameters also provide reproducible estimates of the susceptibility of bacteria to antimicrobial compounds. One such standardized procedure requires the use of standardized inoculum concentrations. This procedure uses paper disks impregnated with 10 mcg of gentamicin to test susceptibility. Results should be interpreted according to the criteria in Table 5.
Table 5: Susceptibility Interpretive Criteria for Gentamicin
Minimum Inhibitory Concentrations (mcg/ml) | Disk Diffusion (Zone diameters in mm) | |||||
|---|---|---|---|---|---|---|
| Pathogen | S | I | R | S | I | R |
| Enterobacteriaceaea | ≤4 | 8 | ≥16 | ≥15 | 13-14 | ≤12 |
| Pseudomonas aeruginosa | ≤4 | 8 | ≥16 | ≥15 | 13-14 | ≤12 |
| Staphylococcus spp. | ≤4 | 8 | ≥16 | ≥15 | 13-14 | ≤12 |
These standards apply to testing done with Mueller-Hinton medium (cation-adjusted for broth) without blood or other nutritional supplements. n/a = not applicable
a-For Salmonella spp. and Shigella spp., gentamicin may appear active in vitro but is not clinically effective
A report of Susceptible indicates that the antimicrobial is likely to inhibit growth of the pathogen if the antimicrobial compound in the blood reaches the concentrations usually achievable. A report of Intermediate indicates that the result should be considered equivocal, and, if the microorganism is not fully susceptible to alternative, clinically feasible drugs, the test should be repeated. This category implies possible clinical applicability in body sites where the drug is physiologically concentrated or in situations where a high dosage of drug can be used or where a prolonged infusion of drug can be used. This category also provides a buffer zone that prevents small, uncontrolled technical factors from causing major discrepancies in interpretation. A report of Resistant indicates that the antimicrobial is not likely to inhibit growth of the pathogen if the antimicrobial compound in the blood reaches the
concentrations usually achievable; other therapy should be selected.
Quality Control
Standardized susceptibility test procedures require the use of quality control microorganisms to control the technical aspects of the test procedures. Standard gentamicin powder should provide the MIC values noted in Table 6. For diffusion techniques using a 10 mcg gentamicin disk, the criteria noted in the table should be achieved.
Table 6: Acceptable Quality Control Ranges for Susceptibility Testing
| QC Organism | Minimum Inhibitory Concentrations (mcg/ml) | Disk Diffusion (zone diameters in mm) |
|---|---|---|
| Escherichia coli ATCC 25922 | 0.25-1 | 19-26 |
| Pseudomonas aeruginosa ATCC 27853 | 0.5-2 | 16-21 |
| Staphylococcus aureus ATCC 29213 | 0.12-1 | n/a |
| Staphylococcus aureus ATCC 25923 | n/a | 19-27 |
These standards apply to testing done with Mueller-Hinton medium (cation-adjusted for broth) without blood or other nutritional supplements.
n/a = not applicable
Synergy/Antagonism with Other Antimicrobials
Aminoglycosides, including gentamicin often exhibit synergistic antimicrobial activity when combined with cell-wall active drugs such as beta-lactams or glycopeptides. This phenomenon forms the basis for the clinical use of aminoglycosides and penicillins as a synergistic combination against certain pathogens. Concomitant exposure of enterococci and certain species of streptococci to a cell wall-active drug such as ampicillin or vancomycin facilitates access of aminoglycosides to their ribosomal target site and this synergy results in an antibacterial effect.
Chemical Interaction with Other Antimicrobials
Cationic aminoglycosides interact chemically with beta-lactam antibiotics with a reaction that results in a nucleophilic opening of the β-lactam ring, with acylation of an amino group of the aminoglycoside and mutual loss of β-lactam antibacterial activity. Therefore penicillin and aminoglycosides should not be mixed in the same solution before infusion.
16. NON-CLINICAL TOXICOLOGY
General Toxicology:
Nephrotoxicity and ototoxicity are the most important adverse effects of aminoglycosides.
Nephrotoxicity
Nephrotoxicity is usually characterized by a fall in glomerular filtration rate (GFR), decreased urinary concentrating capacity, proteinuria, enzymuria and ultrastructural alteration of proximal tubular cells. Although aminoglycosides inhibit Na, K-ATPase activity, it is unlikely that this is the primary mechanism of aminoglycoside nephrotoxicity. The effects of aminoglycosides on mitochondrial and lysosomal function appear to play the main role in aminoglycoside-induced nephrotoxicity.
Rats provide an unusually predictive human surrogate for the nephrotoxicities of aminoglycosides because of the close pharmacokinetic as well as toxicologic similarities of aminoglycosides in rats and humans.
The morphologic lesions of aminoglycoside nephrotoxicity in animals and man are both dose and time dependent. Gross examination at necropsy may reveal some slight mottling of the kidneys in rats given large multiples of the human dose. Histopathologic examination of both kidneys will reveal bilateral proximal tubular damage even at low multiples of the human dose.
Light microscopic changes are usually confined to the S1 and S2 portions of proximal tubules of rats, although glomerular as well as distal and collecting tubular changes have been described in rats by electron microscopy.
Ototoxicity
Ototoxicity was discovered in the first clinical trial of streptomycin in 1945. Tinnitus is a frequent early symptom. Hearing loss occurs as a result of degeneration of the hair cells of the cochlear, beginning at the basal coil and progressing to the apex. High frequency hearing loss is followed by loss of lower frequencies. By the time hearing loss is reported clinically, substantial damage has already occurred.
Both acute and chronic ototoxicity have been observed. The acute type is reversible, while the chronic type may be largely irreversible. The exact mechanisms involved and the relation to the dose and the dosing regimen of aminoglycosides remain unclear, although there are some parallels with the effects in the kidneys: acute reversible hearing loss may relate to competitive antagonism between the drug and calcium; chronic toxicity may relate to aminoglycoside-phosphoinositol binding leading to altered membrane structure and permeability.
Single dose toxicity
Gentamicin has low acute toxicity after oral administration in rodents (LD50 values 8000 to
1000 mg/kg, by weight) but is more toxic following intravenous (LD50 values 37 to 67 mg/kg, by weight) and intramuscular (LD50 values 200 to 890 mg/kg, by weight) administration.
Cationic low molecular weight proteins (LMWP) such as lysozyme and cytochrome c compete for anionic binding sites at the proximal tubule brush border, the first step in endocytic tubular reabsorption. Similar competition between polycationic aminoglycosides appears to take place in the processes of binding to the brush border and subsequent renal accumulation. Since renal absorption of lysozyme takes place via endocytosis, the pharmacological interaction between lysozyme and gentamicin molecules in the early time after gentamicin infusion is very likely to affect tubular reabsorption and intracellular catabolism of lysozyme in the absence of tubular damage.
Isolated rat kidneys were perfused with gentamicin at concentrations of 0.25, 0.50, 1.0 and 2.5 mg/mL. A dose-dependent decrease in percentage reabsorption of lysozyme showed that gentamicin inhibits tubular reabsorption of lysozyme in a dose-dependent manner. Renal catabolism of 125I-lysozyme to smaller degradation products was measured as
nonprecipitable radioactivity (125I and 125I-monoiodotyrosine) released to the perfusate.
Perfusion of the kidneys at a perfusate concentration of gentamicin of 0.5 mg/mL and higher induced almost complete inhibition of renal degradation of lysozyme. This inhibition could be due primarily to inhibition of tubular reabsorption of lysozyme by gentamicin and additionally to the inhibition of enzymatic activity of lysosomal proteases responsible for the lysosomal catabolism of lysozyme.
Repeat dose toxicity
Oral administration of 150 mg/kg/day in rats and 10 mg/kg/day in dogs for one month showed no toxic effects.
Hepatotoxicity has been observed in all animal species studied. Renal tubular degeneration has been documented in rats, monkeys and dogs with doses 2, 8 and 12 times, respectively, above those used in humans.
Treatment of male rats with a toxic dose (30 mg/kg/day) of aminoglycosides for 7, 14 and 21 days demonstrated that only gentamicin and netilmicin decreased glomular filtration rate
(GFR) over the entire treatment period. After 14 days of treatment GFR showed a tendency to return to control in rats treated with netilmicin. No recovery of GFR was observed in gentamicin-treated rats. Gentamicin treatment of Munich-Wistar rats for 10 days at a similar dose (40 mg/kg/day) also induced a significant decrease in glomerular capillary ultrafiltration coefficient (Kf).
Gentamicin and tobramycin alter the ultrastructure of the glomerular endothelium by reducing diameter and frequency of endothelial fenestrae. Glomerular functional and ultrastructural alterations caused by aminoglycoside treatment could be induced through a tubuloglomerular feedback mechanism mediated by the renin-angiotensin system which has been suggested to be related to the pathogenesis of acute renal failure. Consistent with this hypothesis, high doses of gentamicin (120 mg/kg/day) produced a significant increase in plasma renin activity and a concurrent decrease in GFR in rats. Lower doses of gentamicin or tobramycin (30 mg/kg/day) induced an almost complete depletion of cytoplasmic granules from the myoepitheliod cells in the afferent arterial wall of the juxtamedullar apparatus.
Treatment of patients or experimental animals with aminoglycoside antibiotics results in tubular cell injury and necrosis accompanied by enhanced excretion of glucose or of low molecular weight proteins (LMWP) such as β2-microglobulin. These functional alterations suggest an impairment of tubular reabsorptive capacity. Indeed, increased urinary excretion of sodium and potassium are found in aminoglycoside-treated rats.
Aminoglycoside-induced functional alterations were detected by measuring the urinary excretion of the LMWP lysozyme, the lysosomal enzyme N-acetyl-β-D-glucosaminidase and total proteins in intact rats. Gentamicin was more potent than netilmicin in decreasing tubular reabsorption of lysozyme and induced damage to cellular membranes causing leakage of the lysosomal marker enzyme NAG and an increase in total protein excretion.
Tubular reabsorption of lysozyme had a tendency to return toward control despite continued administration of gentamicin or tobramycin. Determination of the glomerular sieving coefficient of lysozyme after aminoglycoside treatment allowed a more accurate quantitation of tubular reabsorption of lysozyme.
Gentamicin and tobramycin (30 mg/kg/day) decreased endocytic reabsorption of lysozyme in isolated perfused kidneys to about 50% after 7 days of treatment. Since aminoglycosides and lysozyme are taken up into tubular cells by endocytosis, it is very likely that the differential effects of aminoglycosides on tubular reabsorption of lysozyme represent specific alterations in proximal tubular function such as impairment of the endocytic protein reabsorption.
In a study by Espandiari et al., 10-, 25-, 40- and 80-day-old rats received a subcutaneous injection of gentamicin at 0, 50, or 100 mg kg-1 body weight per day for 6 or 14 days. 8-day-old rats given the highest dose showed a diminished rate of growth and increase in serum creatinine, blood urea nitrogen, urinary kidney injury molecule-1 and pathological changes. 10- and 40-day-old rats given 100 mg/kg/day of gentamicin for 6 or 14 days also had increased levels of serum blood urea nitrogen and creatinine and renal pathological changes whereas only mild renal changes were found in 25-day-old rats. These findings indicate that clear age-related differences exist in gentamicin-induced renal toxicities and that the neonatal kidney
(25-day-old immature kidney) is more tolerant to the nephrotoxic effects of gentamicin.
Carcinogenicity:
No carcinogenicity studies were available. A report on possible structural similarities of gentamicin and known carcinogens has been compiled. The structural features of gentamicin were compared to those in two lists of structural features that are considered to indicate an increased probability of carcinogenic activity in animals. None of the structural features listed in the two compilations were present in gentamicin.
In addition the Joint WHO/FAO Expert Committee on Food Additives (JECFA) in its evaluation assumed that as no carcinogenic effect has been observed with the other aminoglycosides that have been tested in long-term bioassays in animals, a possible carcinogenic activity of gentamicin is unlikely.
Genotoxicity:
Gentamicin has been tested in a range of in vitro genotoxicity studies (Salmonella microsomal assay, test for mitotic crossing over, gene conversion, DNA repair, Rec-assay) and most gave negative results. However, positive results were noted in in vitro tests for forward mutation in
Escherichia coli at a cytotoxic dose level, in a test for chromosome aberrations in mouse L-cells and in a test for sister chromatid exchange in human fibroblasts. The design of these studies was inadequate to evaluate the genotoxic potential of gentamicin.
Gentamicin was examined for cytotoxicity and mutagenicity in a chromosomal aberration assay in CKO-Kl cells in the absence and presence of metabolic activation. As a result of the cytotoxicity tests, mutagenic activity was tested using final concentrations of 5000, 2000 and
800 mcg/ml. Both positive and negative controls were included. Gentamicin sulfate was negative for inducing chromosomal aberrations in Chinese hamster ovary (CHO) cells, both in presence and absence of metabolic activation.
The mutagenicity of 7 aminoglycoside antibiotics including gentamicin has been studied in cells of the bacteria Salmonella typhimurium and in the yeast Saccharomyces cerevisiae. None of the antibiotics tested demonstrated any mutagenic activities in either the bacteria or the yeast.
In the second study gentamicin sulfate was tested for mutagenic activity in the CHO/HGPRT gene mutation assay. The mutagenic activity was tested using final doses of 5000, 2000, 800,
320 and 128 mcg/ml in the presence and absence of a metabolic activation system. Both negative and positive controls were inc1uded in the study. Gentamicin sulfate was weakly or non-toxic to Chinese hamster ovary cells at concentrations ranging from 8 to 5000 mcg/ml, where cell viability was lower than 50% at 2000 and 5000 mcg/ml. Gentamicin sulfate was negative for inducing a mutagenic response in the CHO/HGPRT gene mutation assay in the presence or in the absence of metabolic activation.
The mutagenic potential of gentamicin sulfate in vivo was investigated in a micronucleus test in bone marrow erythrocytes of CD-l mice. Because of the low absorption of gentamicin after oral administration, the intravenous route was used to ensure exposure of the target bone marrow cells. The mice were dosed at either 20, 40 and 80 mg/kg. No micronucleus induction was detected in bone marrow erythrocytes of any mice treated with the three concentrations of gentamicin. Negative control animals showed normal backgrounds levels of micronuclei and the positive controls animals (cyc1ophosphamide), had substantial increases in the number of bone marrow micronuclei when killed and sampled 24 hours post treatment. Gentamicin sulfate was negative for inducing micronuc1ei in bone marrow cells of CD-l mice when tested to the maximum tolerated intravenous dose of 80 mg/kg.
Although gentamicin gave positive results in some old inadequate in vitro mutagenicity tests, these findings could not be confirmed in a battery of well conducted genotoxicity tests (two in vitro tests (chromosomal aberration assay in CHO-Kl cells, a CHO/HGPRT gene mutation assay)
and one in vivo mouse micronucleus test.
Overall it was concluded that gentamicin is unlikely to be genotoxic.
Reproductive and Developmental Toxicology:
Fetal auditory and vestibular nerve damage may occur. The fetus is at greatest risk during the second and third trimesters.
In pregnant rats treated with intramuscular injection of 75 mg/kg gentamicin for 12 days from day 10 of gestation delivered low birth weight pups 15 hr later than controls. The administration of gentamicin to pregnant rats caused focal tubular lesions in the developing kidney, a reduced rate of early nephrogenesis, and general growth retardation.
In guinea-pigs, intramuscular doses of 4 mg/kg bw/day given on gestation days 48 to 54 did not induce teratogenic effects.
In rabbits after intramuscular administrations of gentamicin at doses of 0.8 and 4 mg/kg bw/day on gestation days 6 to 16, no teratogenic effects were reported.
17. SUPPORTING PRODUCT MONOGRAPHS
- 1. GENTAMICIN INJECTION USP, Solution 10 mg/mL and 40 mg/m, control number 262818, product monograph, Hikma Canada Limited (2022-05-02).