


Product Monograph - Glycopyrrolate Injection USP (Sterimax, 0.4 mg, 4 mg)
CLINICAL PHARMACOLOGY
Glycopyrrolate, like other anticholinergic (antimuscarinic) agents, competitively antagonizes the action of acetylcholine on structures innervated by postganglionic cholinergic nerves and on smooth muscles that respond to acetylcholine but lack cholinergic innervation.
Glycopyrrolate antagonizes muscarinic symptoms ( e.g., bronchorrhea, bronchospasm, bradycardia and intestinal hypermotility) induced by cholinergic drugs such as
anticholinesterases.
As a premedicant, Glycopytrolate Injection USP reduces excessive pharyngeal, tracheal and bronchial secretions and, during anesthesia, it appears to protect the heart against excessive vagal stimulation.
The polar ammonium moiety of glycopyrrolate limits its passage across lipid membranes such as the blood-brain barrier, in contrast to the belladonna alkaloids (such as atropine), which are nonpolar tertiary amines. Consequently, Glycopyrrolate Injection USP does not cause the central nervous system effects seen with the belladonna alkaloids.
The onset of action following intramuscular injection of Glycopyrrolate Injection USP is 20 to
40 minutes. Peak effects occur approximately 30 to 45 minutes after administration and the duration of action ranges from 4 to 6 hours. With intravenous injection, the onset of action is generally evident within one minute; the duration of action varies, as does that of all other anticholinergics. Following intravenous glycopyrrolate, the vagal blocking effects persist for
2 to 3 hours and the antisialagogue effects persist up to 7 hours.
INDICATIONS
Gastrointestinal Disorders: Glycopyrrolate Injection USP may be used in the management of gastrointestinal disorders amenable to anticholinergic therapy when oral medication is not tolerated or a rapid anticholinergic effect is desired.
Anesthesia: Glycopyrrolate Injection USP is of value as a preanesthetic antimuscarinic agent.
During reversal of neuromuscular blockade induced by nondepolarizing muscle relaxants, it protects against the peripheral muscarinic effects (e.g. bradycardia and excessive secretions)
of cholinergic agents such as neostigmine and pyridostigmine.
CONTRAINDICATIONS
Known hypersensitivity to glycopyrrolate.
Due to its benzyl alcohol content, Glycopyrrolate Injection USP when packaged in multidose vials should not be used in newborns.
In addition, in the treatment of gastrointestinal disorders, Glycopyrrolate Injection USP is contraindicated in the presence of glaucoma, obstructive uropathy (for example, bladder neck obstruction due to prostatic hype1trophy), obstructive disease of the gastrointestinal tract (for example, pyloroduodenal stenosis ), paralytic ileus, intestinal atony or chronic lung disease of the elderly or debilitated patient, unstable cardiovascular status in acute hemorrhage, severe ulcerative colitis, toxic megacolon complicating ulcerative colitis, myasthenia gravis.
WARNINGS
Usage in Pregnancy: Use of the drug in pregnancy, lactation or in the childbearing years requires that the potential benefits of the drug be weighed against the possible hazards to mother and child.
In the presence of a high environmental temperature, heat prostration can occur (fever, heat stroke due to decreased sweating) with all anticholinergic agents.
Diarrhea may be an early symptom of incomplete intestinal obstruction, especially in patients with ileostomy or colostomy. In this instance, treatment with this drug would be inappropriate and possibly harmful.
Glycopyrrolate Injection USP may produce drowsiness or blurred vision. In this event, the patients should be warned not to engage in activities requiring mental alertness such as operating a motor vehicle or other machinery, and not to perform hazardous work while taking this drug.
PRECAUTIONS
THE INTRAVENOUS ADMINISTRATION OF ANY ANTICHOLINERGIC IN THE
PRESENCE OF CYCLOPROPANE ANESTHESIA CAN RESULT IN
VENTRICULAR ARRHYTHMIAS; therefore, caution should be observed if
Glycopyrrolate Injection USP must be used during cyclopropane anesthesia. If the drug is given in small incremental doses of 0.1 mg or less, the likelihood of producing ventricular arrhythmias is reduced.
INVESTIGATE ANY TACHYCARDIA BEFORE GIVING ANTICHOLINERGIC
(ATROPINE-LIKE) DRUGS SINCE THEY MAY INCREASE THE HEART RATE.
With overdosage, a curare-like action may occur, i.e. neuromuscular blockade leading to muscular weakness and possible paralysis. However, it has not yet been reported.
Use Glycopyrrolate lnjection USP with caution in the elderly and in all patients with:
- Autonomic neuropathy
- Hepatic or renal disease
- Ulcerative colitis - large doses may suppress intestinal motility to the point of producing a paralytic ileus and for this reason precipitate or aggravate the serious complication of toxic megacolon.
- Hyperthyroidism, coronary heart disease, congestive heart failure, cardiac arrhythmias, hypertension and prostatic hypertrophy.
- Hiatal hernia associated with reflux oesophagitis, since anticholinergic drugs may aggravate this condition.
- Incipient glaucoma (acute glaucoma can be precipitated in susceptible individuals).
It should be noted that the use of anticholinergic drugs in the treatment of gastric ulcer may produce a delay in gastric emptying time and may complicate such therapy (antral stasis). The use of an indwelling nasogastric tube should be considered whenever more than two doses in succession are to be administered.
Do not rely on the use of the drug in the presence of complications of biliary tract disease.
ADVERSE REACTIONS
Adverse reactions to anticholinergics may include xerostomia; urinary hesitancy and retention; blurred vision due to mydriasis and cyclopegia; photophobia; increased ocular tension including acute glaucoma; tachycardia; palpitation; decreased sweating and heat prostration; loss of taste; headache; nervousness; drowsiness, weakness; dizziness, insomnia, nausea; vomiting; impotence; suppression of lactation; constipation; bloated feeling; severe allergic reaction or drug idiosyncrasies including anaphylaxis, urticaria and other dermal manifestations; some degree of mental confusion and/or excitement, especially in elderly persons.
SYMPTOMS AND TREATMENT OF OVERDOSAGE
Symptoms: Widespread paralysis of organs innervated by parasympathetic nerves should create a suspicion of poisoning by antimuscarinic agents. Dry mucous membranes, widely
dilated and unresponsive pupils, tachycardia, cutaneous flush and fever are significant. A curariform neuromuscular block may occur and lead to respiratory paralysis.
Treatment: To combat peripheral anticholinergic effects, a quaternary ammonium anticholinesterase such as neostigmine methylsulfate may be given in a dose of l mg for each mg of Glycopyrrolate Injection USP known to have been administered.
To combat hypotension, pressor amines may be tried. To combat respiratory depression, administer oxygen and respiratory stimulant or artificial respiration. Catheterization sometimes is necessary.
DOSAGE AND ADMINISTRATION
Glycopyrrolate Injection USP may be administered intramuscularly or intravenously, without dilution.
NOT FOR USE IN NEWBORNS WHEN PACKAGED IN MULTIDOSE VIALS.
CHILDREN WITH DISORDERS SUCH AS DOWN'S SYNDROME SHOULD NOT
HAVE ANTICHOLINERGICS, OR IF THEY ARE NECESSARY, THE USUAL DOSE
SHOULD BE REDUCED BY HALF.
Gastroenterology: The usual recommended dose of Glycopyrrolate Injection USP is 0.1 mg administered at 4-hour intervals, three or four times a day. Where a more profound effect is required, 0.2 mg may be given.
Frequency of administration depends upon individual patient response, but a 4-hour interval between injections is recommended. Some patients may need only a single dose; others may require administration two, three or four times a day.
Data on the use of Glycopyrrolate Injection USP in the management of gastrointestinal disorders in children are not available.
Anesthesia: Preanesthetic Medication: Dosage: Adults and Children:
0.005 mg/kg of body weight by intramuscular injection, given 30 minutes to one hour prior to the anticipated time of induction of anesthesia, or at the time the preanesthetic narcotic and/or sedative are administered.
NOTE: CHILDREN (up to 12 years of age) MAY REQUIRE UP TO 0.01 mg/kg OF
BODY WEIGHT.
The timing of administration of Glycopyrrolate Injection USP with relation to the time of anesthetic induction is not as critical as with the belladonna alkaloids, since Glycopyrrolate
Injection USP has a prolonged duration of action, providing protection two to three times as long as that provided by atropine or scopolamine.
| Preanesthetic Dosage 0.005 mg/kg intramuscularly | ||
| Weight | Glycopyrrolate | mL of 0.2 mg/mL strength |
| 10 kg | 0.05 mg | 0.25 mL |
| 20 kg | 0.1 mg | 0.5 mL |
| 30 kg | 0.15 mg | 0.75 mL |
| 40 kg | 0.2 mg | 1.0 mL |
| 50 kg | 0.25 mg | 1.25 mL |
| 60 kg | 0.3 mg | 1.5 mL |
| 70 kg | 0.35 mg | 1.75 mL |
| 80 kg | 0.4 mg | 2.0 mL |
| 90 kg | 0.45 mg | 2.25 mL |
| 100 kg | 0.5 mg | 2.5 mL |
Intraoperative Medication: Glycopyrrolate Injection USP may be used during surgery to counteract drug-induced or vagal traction reflexes with the associated arrhythmias ( e.g., bradycardia). The usual attempts should be made to determine the etiology of the arrhythmia and the surgical or anesthetic manipulations necessary to correct parasympathetic imbalance should be performed.
Dosage: Administer intravenously and repeat as needed at intervals of two to three minutes.
Adults: 0.1 mg. Children: 0.005 mg/kg of body weight, not to exceed 0.1 mg in a single dose.
Reversal of Neuromuscular Blockade: Dosage: Adults and Children: 0.2 mg of
Glycopyrrolate Injection USP for each 1 mg of neostigmine or 5 mg of pyridostigmine.
NOTE: In order to minimize the appearance of cardiac side effects, the drugs may be administered simultaneously by intravenous injection and may be mixed in the same syringe.
Mixtures containing more than 5 mg of neostigmine or 25 mg of pyridostigmine plus 1 mg of glycopyrrolate are not recommended.
PHARMACEUTICAL INFORMATION
DRUG SUBSTANCE
Proper Name: Glycopyrrolate
Chemical name: (3RS)-3-[(2SR) – (2-Cyclopentyl-2-hydroxy-2-phenylacetyl)
oxy] 1, 1-dimethylpyrrolidinium bromide
Structural Formula:
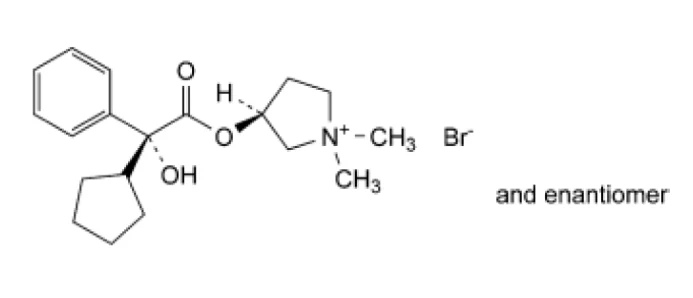
Molecular Formula: C19H28BrN03
Molecular Weight: 398.35
Description: White, odorless, crystalline powder, soluble in water and alcohol, with a melting point of 193 to 198°C.
COMPOSITION:
Single Use Vial: Each mL contains glycopyrrolate 0.2 mg, sodium chloride 8.5 mg, hydrochloric acid and/or sodium hydroxide to adjust pH (pH 2-3), and water for injection.
Multidose Vial: Each mL contains glycopyrrolate 0.2 mg, sodium chloride 7.47 mg, benzyl alcohol (as a preservative) 0.9%, hydrochloric acid and/or sodium hydroxide to adjust pH (pH
2-3), and water for injection.
STABILITY AND STORAGE RECOMMENDATIONS:
Store between 15°C and 30°C.
Multidose Vial: Discard 28 days after initial puncture.
AVAILABILITY OF DOSAGE FORMS
Glycopyrrolate Injection USP is available in 1 mL and 2 mL single use glass vials with chlorobutyl rubber stoppers, boxes of 10 and in 20 mL multidose vials, boxes of 1.
Latex-Free Stoppers: Stoppers contain no dry natural rubber latex.
ANIMAL PHARMACOLOGY
A variety of basic pharmacological studies in animals have demonstrated that glycopyrrolate consistently antagonizes parasympathetically-mediated effects. In dogs, it inhibited basal and histamine-stimulated gastric secretion, and was effective in blocking the enhanced secretion resulting from insulin-induced hypoglycemia. Intestinal tone was reduced at dosages which produced little or no effect on peristaltic movements.
In addition to its gastric antisecreto1y action, glycopyrrolate inhibited salivary secretion induced by methacholine in the anesthetized dog. Methacholine-induced lacrimation in rats was also blocked.
The poor penetration of glycopyrrolate into the CNS was demonstrated in EEG studies in unanesthetized curarized cats. Further confirmation of the lack of a central (CNS) effect was demonstrated in antitremorine studies in mice. In anesthetized dogs, intravenous doses had essentially no effect on respiration, carotid arterial blood pressure or cardiac rate. Likewise, these doses of glycopyrrolate reduced bradycardia, hypotension and the intestinal hyperactivity resulting from peripheral vagal stimulation. Other than the expected parasympathetic inhibition, no effects on the autonomic nervous system were observed.
TOXICOLOGY
Acute Toxicity: LD50 values were determined by intravenous, intraperitoneal and oral administration in the mouse, and by intravenous administration in the rat and the rabbit. The following table shows the results.
Acute toxicity of Glycopyrrolate Species Sex Route LD50 mg/kg
Mouse M IV 15 Mouse M IP 112 Mouse M Oral 550 Rat F IV 15 Rabbit M,F IV 25* *Approximate
Higher doses by all routes in mice and rats caused mydriasis, tremors and tonic and clonic convulsions. Death usually followed the convulsions and apparently resulted from respiratory failure. In rabbits, all animals exhibited mydriasis, tachycardia and prostration. All survivors appeared normal at 72 hours. No outstanding gross pathological changes attributable to glycopyrrolate were found in the survivors or the animals that died.
Four-week Toxicity: The intravenous administration of Glycopyrrolate at 2.0 or 0.4 mg/kg/day five days a week for four weeks caused no signs of toxicity in beagle dogs.
Evaluations included body weight gain, hemograms, gross and microscopic examination of tissues, blood nitrogen, serum alkaline phosphatase, serum glutamic oxalacetic transaminase and qualitative urinalysis.
Irritation Potential: Repeated intramuscular injection of glycopyrrolate into the hind leg of the rabbit, or topical application of glycopyrrolate solutions to the abraded or intact skin of the rabbit did not induce a reaction sufficient to preclude use of the injectable material. No histological evidence of inflammation was observed following subcutaneous injection of glycopyrrolate in the rabbit.
Reproductive Studies: Reproductive studies in rats and rabbits revealed no teratogenic effects from glycopyrrolate. However, diminished rates of conception and of survival at weaning were observed in rats, in a dose-related manner. Studies in dogs suggest that this may be due to diminished seminal secretion which is evident at high doses of glycopyrrolate.
REFERENCES
- 1.
Ali-Melkkila TM, Kaila T, Kanto J, Iisalo E. Pharmacokinetics of I.M.
Glycopyrronium. Br J Anaesth 1990; 64:667-669.
- 2.
Dodd P, Day SJ, Goldhill DR, MacLeod DM, Withington PS, Yate PM.
Glycopyrronium requirements for antagonism of the muscarinic side effects of edrophonium. Br J Anaesth 1989; 62:77-81.
- 3.
Grum DF, Osborne LR. Central Anticholinergic Syndrome following Glycopyrrolate.
Anesthesiology 1991; 74:191-193.
- 4. Mirakhur RK. Premedication with atropine or glycopyrrolate in children. Effects on heart rate and rhythm during induction and maintenance of anaesthesia. Anaesthesia 1982; 37:1032-1036.
- 5. Mirakhur RK. Antagonism of neuromuscular block in the elderly. A comparison of atropine and glycopyrronium in a mixture with neostigmine. Anaesthesia 1985; 40:254-258.
- 6.
Mirakhur RK, Dundee JW. Glycopyrrolate: pharmacology and clinical use.
Anaesthesia 1983; 38:1195-1204.
- 7. Mostafa SM, Vucevic M. Comparison of atropine and glycopyrronium in patients with pre-existing cardiac disease. Anaesthesia 1984; 39:1207-1213.
- 8. Salem MG, Richardson JC, Meadows GA, Lamplugh G, Lai KM. Comparison between glycopyrrolate and atropine in a mixture with neostigmine for reversal of neuromuscular blockade. Br J Anaesth 1985; 57:184-187.
- 9.
Shamsai J. Central Anticholinergic Syndrome: Does it Exist? Anesthesiology 1991;
74: 1158.
- 10.
Sheref SE. Pattern of CNS recovery following reversal of neuromuscular blockade.
Br J Anaesth 1985; 57:188-191.
- 11.
Slovis CM, Daniels GM, Wharton DR. Intravenous Use of Glycopyrrolate in Acute
Respiratory Distress Due to Bronchospastic Pulmonary Disease. Ann Emerg Med 1987; 16:898-900.
- 12.
Wingard DW. Glycopyrrolate and the Central Anticholinergic Syndrome.
Anesthesiology 1991; 75:1125-1126.
- 13.
Product Monograph, Glycopyrrolate Injection USP. Sandoz Canada Inc, August 18,
2005. Control number 100418.