


Product Monograph - Hp-Pac
SUMMARY PRODUCT INFORMATION
Route of Administration | Dosage Form / Strength | Non-medicinal Ingredients |
| oral | Lansoprazole delayed-release capsules / 30 mg Clarithromycin film-coated tablets / 500 mg Amoxicillin capsules / 500 mg | Colloidal silicon dioxide, D&C Red No. 28, FD&C Blue No. 1, FD&C Red No. 40, gelatin, hydroxypropyl cellulose, low substituted hydroxypropyl cellulose, magnesium carbonate, methacrylic acid copolymer, polyethylene glycol, polysorbate 80, starch, sucrose, sugar spheres, talc and titanium dioxide. Cellulosic polymers, croscarmellose sodium, D&C Yellow No. 10, magnesium stearate, povidone, propylene glycol, silicon dioxide, sorbic acid, sorbitan monooleate, stearic acid, talc, titanium dioxide and vanillin. Colloidal silicon dioxide, ECG size #0, dry-flo starch, magnesium stearate, sodium lauryl sulfate, and talc. This is a complete listing of non-medicinal ingredients. |
INDICATIONS AND CLINICAL USE
The components of the Hp-PAC® [PREVACID® (lansoprazole delayed-release capsules), in combination with clarithromycin film-coated tablets plus amoxicillin capsules as triple therapy], are indicated for:
- the treatment of patients with Helicobacter pylori (H. pylori) infection and active duodenal ulcer disease. Eradication of H. pylori has been shown to reduce the risk of duodenal ulcer recurrence (see CLINICAL TRIALS and DOSAGE AND ADMINISTRATION).
In patients with a recent history of duodenal ulcers who are H. pylori positive, eradication therapy may reduce the rate of recurrence of duodenal ulcers. The optimal timing for eradication therapy for such patients remains to be determined.
In patients who fail a therapy combination containing clarithromycin, susceptibility testing should be done. If resistance to clarithromycin is demonstrated or susceptibility testing is not possible, an alternative therapy combination is recommended.
Resistance to amoxicillin has not been demonstrated in clinical studies with lansoprazole delayed-release capsules and amoxicillin.
Table 1 summarizes the eradication rates for the H. pylori Triple Therapy treatment regimen.
Table 1. Eradication Rates for the H. pylori Triple Therapy Treatment Regimens
Treatment Regimen
Days/ Study No. | Evaluable (Per Protocol)* % (n/N) | ITT (all data)† % (n/N) |
ITT
(Worst Case)‡
% (n/N)
PREVACID® 30 mg capsules/ clarithromycin 500 mg/ amoxicillin 1000 mg (all twice daily)
| 14/ M93-131 | 92 (44/48) | 94 (47/50) |
86 (47/55)
14/ M95-392 | 86 (57/66) | 87 (58/67) |
83 (58/70)
PREVACID® 30 mg capsules/ clarithromycin 500 mg/ amoxicillin 1000 mg (all twice daily)
10/ M95-399 | 84 (103/123) | 86 (110/128) |
81 (110/135)
PREVACID® 30 mg capsules/ clarithromycin 250 mg/ amoxicillin 1000 mg (all twice daily)
7/ GB 94/110 | 90 (103/114) | 90 (104/116) |
86 (104/121)
Definitions: ITT = intent-to-treat patients
* Based on evaluable patients with confirmed duodenal ulcer and/or gastritis and H. pylori infection at baseline defined as at least 2 of 3 positive endoscopic tests from CLOtest®, histology and/or culture. Patients were included in the analysis if they completed the study. Additionally, if patients dropped out of the study due to an adverse event related to the study drug, they were included in the analysis as failures of therapy.
† Patients were included in the analysis if they had documented H. pylori infection at baseline as defined above and had a confirmed duodenal ulcer.
‡ “Worst case” included patients with no available data as failures.
Patients were included in the analysis if they had documented duodenal ulcer (active) and H. pylori infection at baseline defined as at least 2 of 3 positive endoscopic tests from CLOtest®, histology and/or culture.
To reduce the development of drug-resistant bacteria and maintain the effectiveness of BIAXIN BID® or amoxicillin capsules and other antibacterial drugs, BIAXIN BID® or amoxicillin capsules should be used only to treat infections that are proven or strongly suspected to be caused by susceptible bacteria. When culture and susceptibility information are available, they should be considered in selecting or modifying antibacterial therapy. In the absence of such data, local epidemiology and susceptibility patterns may contribute to the empiric selection of therapy.
CONTRAINDICATIONS
Patients with known hypersensitivity to any component of the formulations of
PREVACID®; clarithromycin, erythromycin, or any macrolide antibiotic; or amoxicillin or other beta-lactam antiobiotics (e.g., any penicillin or cephalosporin). For a complete listing, see the DOSAGE FORMS, COMPOSITION AND PACKAGING section of the product monograph.
- Clarithromycin is contraindicated in patients with a history of cholestatic jaundice/hepatic dysfunction associated with prior use of clarithromycin.
- Clarithromycin is contraindicated in patients who suffer from severe hepatic failure in combination with renal impairment. See WARNINGS AND PRECAUTIONS, Hepatic/Biliary/Pancreatic and WARNINGS AND PRECAUTIONS, Renal.
- Clarithromycin is contraindicated in patients with history of QT prolongation or ventricular cardiac arrhythmia, including torsades de pointes. See WARNINGS AND PRECAUTIONS and DRUG INTERACTIONS, Table 7.
- Patients with hypokalaemia due to the risk of prolongation of QT-time and torsades de pointes.
- Clarithromycin is contraindicated as concomitant therapy with astemizole, cisapride, pimozide, terfenadine. There have been post-marketing reports of drug interactions when clarithromycin and/or erythromycin are co-administered with astemizole, cisapride, pimozide, or terfenadine resulting in cardiac arrhytmias (QT prolongation, ventricular tachycardia, ventricular fibrillation, and torsades de pointes) most likely due to inhibition of hepatic metabolism of these drugs by erythromycin and clarithromycin. Fatalities have been reported (see DRUG INTERACTIONS).
Clarithromycin should not be used concomitantly with HMG-CoA reductase inhibitors
(statins) that are extensively metabolized by CYP3A4 (lovastatin or simvastatin), due to an increased risk of myopathy, including rhabdomyolysis. See DRUG INTERACTIONS, Table 7.
Clarithromycin is contraindicated as concomitant therapy with ergot alkaloids
(e.g., ergotamine or dihydroergotamine) as this may result in ergot toxicity. See DRUG INTERACTIONS, Table 7.
Clarithromycin is contraindicated as concomitant therapy with oral midazolam. See
DRUG INTERACTIONS, Table 7.
- Clarithromycin is contraindicated as concomitant therapy with colchicine due to the risk of life threatening and fatal colchicine toxiciy. This risk may be further increased with concomitant medications metabolized by P-glycoprotein or strong CYP3A inhibitors. See DRUG INTERACTIONS, Table 7.
Clarithromycin is contraindicated as concomitant therapy with ticagrelor or ranolazine*.
* Not marketed in Canada.
Clarithromycin is contraindicated as concomitant therapy with saquinavir/ritonavir. See
DRUG INTERACTIONS, Table 7.
- Amoxicillin is contraindicated in cases where infectious mononucleosis is either suspected or confirmed.
Co-administration with rilpivirine is contraindicated. See DRUG INTERACTIONS,
Table 6.
For information on the use of the individual components of the Hp-PAC® when dispensed as individual medications outside the combined use for the treatment of Helicobacter pylori (H. pylori), the respective Product Monographs for these products should be consulted.
WARNINGS AND PRECAUTIONS
Serious Warnings and Precautions
- Clarithromycin should not be used in pregnancy except where no alternative therapy is appropriate, particularly during the first 3 months of pregnancy. If pregnancy occurs while taking the drug, the patient should be apprised of the potential hazard to the fetus. Clarithromycin has demonstrated adverse effects on pregnancy outcome and/or embryo-fetal development in monkeys, mice, rats and rabbits at doses that produced plasma levels 2 to 17 times the serum levels obtained in humans treated at the maximum recommended doses (see WARNINGS AND PRECAUTIONS section in the Clarithromycin Product Monograph).
The concomitant administration of clarithromycin and drugs metabolized by
CYP3A and/or transported by P-gp may result in significant safety concerns. See DRUG INTERACTIONS.
- Serious and occasionally fatal hypersensitivity (anaphylactic) reactions have been reported in patients on penicillin therapy. These reactions are more apt to occur in individuals with a history of penicillin hypersensitivity and/or a history of sensitivity to multiple allergens.
There have been well documented reports of individuals with a history of penicillin hypersensitivity reactions who have experienced severe hypersensitivity reactions when treated with a cephalosporin. Before initiating therapy with any penicillin, careful inquiry should be made concerning previous hypersensitivity reactions to penicillins, cephalosporins, and other allergens. If an allergic reaction occurs, amoxicillin should be discontinued and the appropriate therapy instituted.
Serious anaphylactoid reactions require immediate emergency treatment with epinephrine. Oxygen, intravenous steroids, and airway management, including intubation, should also be administrered as indicated.
General
H. pylori Eradication and Compliance
To avoid failure of the eradication treatment with a potential for developing antimicrobial resistance and a risk of failure with subsequent therapy, patients should be instructed to follow closely the prescribed regimen.
For the eradication of H. pylori, amoxicillin and clarithromycin should not be administered to patients with renal impairment since the appropriate dosage in this patient population has not yet been established.
The possibility of superinfections with fungal organisms or bacterial pathogens should be considered during therapy. In such cases, discontinue Hp-PAC® and substitute appropriate treatment.
PREVACID® (lansoprazole delayed-release capsules)
Symptomatic response to therapy with lansoprazole does not preclude the presence of gastric malignancy.
Literature suggests that concomitant use of PPIs with methotrexate (primarily at high dose) may elevate and prolong serum levels of methotrexate and/or its metabolite, possibly leading to methotrexate toxicities. A temporary withdrawal of the PPI may be considered in some patients receiving treatments with high dose methotrexate (see DRUG INTERACTIONS).
Drug Interactions with Antiretroviral Drugs
PPIs have been reported to interact with some antiretroviral drugs. The clinical importance and the mechanisms behind these interactions are not always known. A change in gastric pH may change the absorption of the antiretroviral drug. Other possible mechanisms are via CYP 2Cl9.
Rilpivirine
Co-administration is contraindicated due to significant decrease in rilpivirine exposure and loss of therapeutic effect (see CONTRAINDICATIONS).
Atazanavir and Nelfinavir
Co-administration with atazanavir or nelfinavir is not recommended due to decreased atazanavir and nelfinavir exposure (see the REYATAZ® and VIRACEPT® Product Monographs).
If the combination of Hp-PAC® with atazanavir is judged unavoidable, close clinical monitoring is recommended in combination with the use of 400 mg atazanavir/100 mg ritonavir dose (see REYATAZ® Product Monograph).
Saquinavir
If Hp-PAC® is co-administered with saquinavir/ritonavir, caution and monitoring for potential saquinavir toxicities, including gastrointestinal symptoms, increased triglycerides, deep vein thrombosis and QT prolongation, are recommended. Dose reduction of saquinavir should be considered from the safety perspective for individual patients (see INVIRASE® Product Monograph).
Bone Fracture
Several published observational studies suggest that PPI therapy may be associated with an increased risk for osteoporosis-related fractures of the hip, wrist, or spine. The risk of fracture was increased in patients who received high-dose, defined as multiple daily doses, and long-term PPI therapy (a year or longer). Patients should use the lowest dose and shortest duration of PPI therapy appropriate to the condition being treated. Patients at risk for osteoporosis-related fractures should be managed according to established treatment guidelines (see DOSAGE AND ADMINISTRATION and ADVERSE REACTIONS).
BIAXIN BID® (clarithromycin tablets, USP, film-coated)
Clarithromycin should be administered with caution to any patient who has demonstrated some form of drug allergy, particularly to structurally-related drugs. If an allergic reaction to clarithromycin occurs, administration of the drug should be discontinued. Serious hypersensitivity reactions may require epinephrine, antihistamines, or corticosteroids. See WARNINGS AND PRECAUTIONS, Immune, Hypersensitivity.
Myasthenia Gravis
Exacerbation of symptoms of myasthenia gravis and new onset of symptoms of myasthenic syndrome has been reported in patients receiving clarithromycin therapy.
AMOXICILLIN (amoxicillin trihydrate) Capsules
Periodic assessment of renal, hepatic and hematopoietic functions should be made during prolonged therapy with Amoxicillin (amoxicillin trihydrate).
Abnormal prolongation of prothrombin time (increased international normalized ratio (INR)) has been reported in patients receiving amoxicillin and oral anticoagulants. See DRUG INTERACTIONS.
Carcinogenesis and Mutagenesis
PREVACID® (lansoprazole delayed-release capsules)
Safety concerns of long-term treatment relate to hypergastrinemia, possible enterochromaffin-like (ECL) effect and carcinoid formation. ECL cell hyperplasia and gastric carcinoid tumours
were observed in 4 animal studies. See TOXICOLOGY, Mutagenicity and Carcinogenesis for further details.
Analysis of gastric biopsy specimens from patients after short-term treatment of proton pump inhibitors have not detected ECL cell effects similar to those seen in animal studies. Longer term studies in humans revealed a slight increase in the mean ECL-cell density, although there was no microscopic evidence of cell hyperplasia. Similar results were seen in the maintenance treatment studies, where patients received up to 15 months of lansoprazole therapy. Serum gastrin values increased significantly from their baseline values but reached a plateau after two months of therapy. By one month post-treatment, fasting serum gastrin values returned to lansoprazole therapy baseline. Moreover, results from gastric biopsies from short-term, long-term and maintenance treatment studies indicate that there are no clinically meaningful effects on gastric mucosa morphology among lansoprazole-treated patients. For further details, see information under DETAILED PHARMACOLOGY and TOXICOLOGY.
BIAXIN BID® (clarithromycin tablets, USP, film-coated)
Long-term studies in animals have not been performed to evaluate the carcinogenic potential of clarithromycin.
The following in vitro mutagenicity tests have been conducted with clarithromycin: Salmonella/mammalian microsome test, bacterial induced mutation frequency test, in vitro chromosome aberration test, rat hepatocyte DNA synthesis assay, mouse lymphoma assay, mouse dominant lethal study, mouse micronucleus test. All tests had negative results except the in vitro chromosome aberration test which was weakly positive in one test and negative in another. In addition, a Bacterial Reverse-Mutation Test (Ames Test) has been performed on clarithromycin metabolites with negative results.
AMOXICILLIN (amoxicillin trihydrate) Capsules
Long-term studies in animals have not been performed to evaluate the carcinogenic potential of amoxicillin. Studies to detect mutagenic potential of amoxicillin alone have not been conducted.
Cardiovascular
BIAXIN BID® (clarithromycin tablets, USP, film-coated)
Clarithromycin should be used with caution in patients with coronary artery disease, severe cardiac insufficiency, hypomagnesemia, bradycardia (< 50 bpm), or when co-administered with other medicinal products associated with QT prolongation, due to the risk for QT prolongation and torsades de pointes. See DRUG INTERACTIONS.
Clarithromycin is contraindicated in patients with congenital or documented acquired QT prolongation or history of ventricular arrhythmia, including torsades de pointes. Clarithromycin is also contraindicated in patients with hypokalaemia due to the risk of QT prolongation and torsades de pointes. See CONTRAINDICATIONS.
Endocrine and Metabolism
PREVACID® (lansoprazole delayed-release capsules)
Hypomagnesemia
Hypomagnesemia, symptomatic and asymptomatic, has been reported rarely in patients treated with PPIs for at least three months, in most cases after a year of therapy. Serious adverse events include tetany, arrhythmias, and seizures. In most patients, treatment of hypomagnesemia required magnesium replacement and discontinuation of the PPI.
For patients expected to be on prolonged treatment or who take PPIs with medications such as digoxin or drugs that may cause hypomagnesemia (e.g., diuretics), health care professionals may consider monitoring magnesium levels prior to initiation of PPI treatment and periodically (see ADVERSE REACTIONS).
The chronic use of PPIs may lead to hypomagnesemia. Moreover, hypokalemia and hypocalcemia have been reported in the literature as accompanying electrolyte disorders.
Cyanocobalamin (Vitamin B12) Deficiency
The prolonged use of proton pump inhibitors may impair the absorption of protein-bound Vitamin B12 and may contribute to the development of cyanocobalamin (Vitamin B12) deficiency.
Interference with Laboratory Tests
During treatment with antisecretory drugs, chromogranin A (CgA) increases due to decreased gastric acidity. Increased CgA levels may interfere with investigations for neuroendocrine tumours. To avoid this interference, Hp-PAC® treatment should be stopped 14 days before CgA measurements (see DRUG INTERACTIONS).
Gastrointestinal
PREVACID® (lansoprazole delayed-release capsules)
When gastric ulcer is suspected, the possibility of malignancy should be excluded before therapy with PREVACID® is instituted as treatment with this drug may alleviate symptoms and delay diagnosis.
Clostridium Difficile-Associated Diarrhea
Decreased gastric acidity due to any means, including proton pump inhibitors (PPIs), increases gastric counts of bacteria normally present in the gastrointestinal tract. Treatment with proton pump inhibitors can lead to an increased risk of gastrointestinal infections such as Salmonella, Campylobacter and Clostridium difficile.
An increased risk for Clostridium difficile infection (CDI) and Clostridium difficile-associated diarrhea (CDAD) has been observed in association with PPI use in several observational studies. CDI/CDAD should be considered in the differential diagnosis for diarrhea that does not improve. Additional risk factors for CDI and CDAD include recent hospitalization, the use of antibiotics, old age and the presence of co-morbidities.
Patients should be prescribed PPIs at the lowest dose and for the shortest duration required for the condition being treated and be reassessed to ascertain whether continued PPI therapy remains beneficial.
BIAXIN BID® (clarithromycin tablets, USP, film-coated) / AMOXICILLIN (amoxicillin trihydrate) Capsules
Clostridium difficile-associated disease (CDAD) has been reported with use of many antibacterial agents, including clarithromycin and amoxicillin. CDAD may range in severity from mild diarrhea to fatal colitis. It is important to consider this diagnosis in patients who present with diarrhea, or symptoms of colitis, pseudomembranous colitis, toxic megacolon, or perforation of colon subsequent to the administration of any antibacterial agent. CDAD has been reported to occur over 2 months after the administration of antibacterial agents.
Treatment with antibacterial agents may alter the normal flora of the colon and may permit overgrowth of Clostridium difficile. C. difficile produces toxins A and B, which contribute to the development of CDAD. CDAD may cause significant morbidity and mortality. CDAD can be refractory to antimicrobial therapy.
If the diagnosis of CDAD is suspected or confirmed, appropriate therapeutic measures should be initiated. Mild cases of CDAD usually respond to discontinuation of antibacterial agents not directed against Clostridium difficile. In moderate to severe cases, consideration should be given to management with fluids and electrolytes, protein supplementation, and treatment with an antibacterial agent clinically effective against Clostridium difficile. Surgical evaluation should be instituted as clinically indicated, as surgical intervention may be required in certain severe cases. See ADVERSE REACTIONS.
Genitourinary
PREVACID® (lansoprazole delayed-release capsules)
In the 24-month toxicology study in rats, after 18 months of treatment, Leydig cell hyperplasia increased above the concurrent and historical control level at dosages of 15 mg/kg/day or higher (see TOXICOLOGY).
Testicular interstitial cell adenoma also occurred in 1 of 30 rats treated with 50 mg/kg/day (13 times the recommended human dose based on body surface area) in a 1-year toxicity study (see TOXICOLOGY).
These changes are associated with endocrine alterations which have not been, to date, observed in humans. For further details, see information under DETAILED PHARMACOLOGY and TOXICOLOGY.
Hepatic/Biliary/Pancreatic
PREVACID® (lansoprazole delayed-release capsules)
It is recommended that the initial dosing regimen need not be altered for patients with mild or moderate liver disease, but for patients with moderate impairment, doses higher than 30 mg / day should not be administered unless there are compelling clinical indications. Dose reduction in patients with severe hepatic disease should be considered.
BIAXIN BID® (clarithromycin tablets, USP, film-coated)
Caution is advised in patients with impaired hepatic function.
Clarithromycin is principally excreted by the liver and kidney. In patients with a combination of hepatic (mild to moderate) and renal impairments, decreased dosage of clarithromycin or prolonged dosing intervals might be appropriate.
Clarithromycin is contraindicated in patients with severe hepatic failure in combination with renal impairment. See CONTRAINDICATIONS.
Hepatic dysfunction, including increased liver enzymes, and hepatocellular and/or cholestatic hepatitis, with or without jaundice, has been reported with clarithromycin. This hepatic dysfunction may be severe and is usually reversible. In some instances, hepatic failure with fatal outcomes has been reported and generally has been associated with serious underlying diseases and/or concomitant medications. Discontinue clarithromycin immediately if signs and symptoms of hepatitis occur, such as anorexia, jaundice, dark urine, pruritus, or tender abdomen.
Immune
In the event of severe acute hypersensitivity reactions, such as anaphylaxis, Stevens-Johnson Syndrome, toxic epidermal necrolysis, drug rash with eosinophilia and systemic symptoms (DRESS), and Henoch-Schonlein purpura, Hp-PAC® should be discontinued immediately and appropriate treatment should be urgently initiated.
PREVACID® (lansoprazole delayed-release capsules)
Subacute cutaneous lupus erythematosus
Subacute cutaneous lupus erythematosus (SCLE) has been reported with the use of PPIs. If lesions occur, especially in sun-exposed areas of the skin, and if accompanied by arthralgia, the patient should seek medical help promptly and the health care professional should consider stopping Hp-PAC®. The occurrence of SCLE with previous PPI treatment may increase the risk
of SCLE with other PPIs (see ADVERSE REACTIONS, Post-Market Adverse Drug Reactions).
BIAXIN BID® (clarithromycin tablets, USP, film-coated)
Severe acute hypersensitivity reactions (including anaphylaxis) have been reported in patients receiving clarithromycin orally.
AMOXICILLIN (amoxicillin trihydrate) Capsules
Serious and occasionally fatal hypersensitivity (anaphylactic) reactions have been reported in patients on penicillin therapy, including amoxicillin. Although anaphylaxis is more frequent following parenteral therapy, it has occurred in patients on oral penicillins. These reactions are more likely to occur in individuals with a history of penicillin hypersensitivity and/or a history of sensitivity to multiple allergens. There have been reports of individuals with a history of penicillin hypersensitivity who have experienced severe reactions when treated with cephalosporins. Before initiating therapy with Hp-PAC®, careful inquiry should be made regarding previous hypersensitivity reactions to penicillins, cephalosporins, or other allergens.
A morbilliform rash following the use of ampicillin in patients with infectious mononucleosis has been well documented and has also been reported to occur following the use of amoxicillin.
Ophthalmologic
PREVACID® (lansoprazole delayed-release capsules)
Retinal atrophy
In animal studies, retinal atrophy was observed in rats dosed orally for 2 years with lansoprazole at doses of 15 mg/kg/day and above. These changes in rats are believed to be associated with the effects of taurine imbalance and phototoxicity in a susceptible animal model.
Clinical data available from long-term PREVACID® studies are not suggestive of any drug-induced eye toxicity in humans. In humans, there are presently no concerns for ocular safety with short-term lansoprazole treatment and the risks associated with long-term use for nearly 5 years appear to be negligible.
The finding of drug-induced retinal atrophy in the albino rat is considered to be species-specific with little relevance for humans. For further details, see information under DETAILED PHARMACOLOGY and TOXICOLOGY.
Renal
Hp-PAC® Triple Therapy: PREVACID®/clarithromycin/amoxicillin
For the eradication of H. pylori, amoxicillin and clarithromycin should not be administered to patients with renal impairment since the appropriate dosage in this patient population has not yet been established.
PREVACID® (lansoprazole delayed-release capsules)
No dosage adjustment of lansoprazole is necessary in patients with renal impairment. See DOSAGE AND ADMINISTRATION and ACTION AND CLINICAL PHARMACOLOGY.
BIAXIN BID® (clarithromycin tablets, USP, film-coated)
Caution is advised in patients with severe renal insufficiency.
Clarithromycin is principally excreted by the liver and kidney (see DOSAGE AND ADMINISTRATION).
In patients with a combination of hepatic (mild to moderate) and renal impairments or in the presence of severe renal impairment, decreased dosage of clarithromycin or prolonged dosing intervals might be appropriate. For dosage adjustment recommendations, refer to the Clarithromycin Product Monograph.
Clarithromycin is contraindicated in patients with severe hepatic failure in combination with renal impairment. See CONTRAINDICATIONS.
AMOXICILLIN (amoxicillin trihydrate) Capsules
Amoxicillin is excreted mostly by the kidney; the dosage for patients with renal impairment should be reduced in proportion to the degree of loss of renal function (see DOSAGE AND ADMINISTRATION).
Susceptibility/Resistance
Antibiotic Resistance in Relation to H. pylori Eradication
To avoid failure of the eradication treatment with a potential for developing antimicrobial resistance and a risk of failure with subsequent therapy, patients should be instructed to follow closely the prescribed regimen.
Development of Drug Resistant Bacteria
Prescribing BIAXIN BID® or amoxicillin capsules in the absence of a proven or strongly suspected bacterial infection is unlikely to provide benefit to the patient and risks the development of drug-resistant bacteria.
BIAXIN BID® (clarithromycin tablets, USP, film-coated)
Use of any antimicrobial therapy, such as clarithromycin, to treat H. pylori infection may select for drug-resistant organisms.
Three patients [3/82 (3.7%)] who had isolates susceptible to clarithromycin pretreatment and were treated with the triple therapy regimen remained H. pylori positive post-treatment. None of the isolates from these 3 patients had susceptibility results available after treatment with triple therapy; therefore, it is unknown whether or not these patients developed resistance to clarithromycin. Sixteen percent of the patients treated with the dual therapy regimen developed clarithromycin resistance post-treatment. Therefore, development of clarithromycin resistance should be considered as a possible risk.
AMOXICILLIN (amoxicillin trihydrate) Capsules
If superinfections with mycotic or bacterial pathogens occur (usually involving Aerobacter, Pseudomonas or Candida) treatment with Amoxicillin should be discontinued and appropriate therapy instituted.
Use in Women
Over 4,000 women were treated with lansoprazole. Ulcer healing rates in females were similar to those in males. The incidence rates of adverse events are also similar to those seen in males.
Special Populations
Pregnant Women
PREVACID® (lansoprazole delayed-release capsules)
Reproductive studies conducted in pregnant rats at oral doses up to 150 mg/kg/day (40 times the recommended human dose based on body surface area), and in rabbits at oral doses up to 30 mg/kg/day (16 times the recommended human dose based on body surface area), revealed no lansoprazole-related impairment of fertility, fetal malformations or developmental toxicity to fetuses or suckling neonates. Lansoprazole is not considered to be teratogenic. Maternal toxicity and a significant increase in fetal mortality were observed in the rabbit study at doses above 10 mg/kg/day. In rats, maternal toxicity and a slight reduction in litter survival and weights were noted at doses above 100 mg/kg/day. See TOXICOLOGY, Reproduction and Teratology.
There are no adequate or well-controlled studies in pregnant women. Therefore, lansoprazole should be used with caution during pregnancy, only if the potential benefit justifies the potential risk to the fetus.
BIAXIN BID® (clarithromycin tablets, USP, film-coated)
There are no adequate and well-controlled studies in pregnant women. The benefits against risk, particularly during the first 3 months of pregnancy should be carefully weighed by a physician (see WARNINGS AND PRECAUTIONS). Four teratogenicity studies in rats (3 with oral doses and 1 with intravenous doses up to 160 mg/kg/day administered during the period of major organogenesis) and 2 in rabbits (at oral doses up to 125 mg/kg/day or intravenous doses of 30 mg/kg/day administered during gestation days 6 to 18) failed to demonstrate any teratogenicity from clarithromycin. Two additional oral studies in a different rat strain at similar doses and similar conditions demonstrated a low incidence of cardiovascular anomalies at doses of 150 mg/kg/day administered during gestation days 6 to 15. Plasma levels after 150 mg/kg/day were 2 times the human serum levels.
Four studies in mice revealed a variable incidence of cleft palate following oral doses of 1000 mg/kg/day during gestation days 6 to 15. Cleft palate was also seen at 500 mg/kg/day. The 1000 mg/kg/day exposure resulted in plasma levels 17 times the human serum levels. In monkeys, an oral dose of 70 mg/kg/day produced fetal growth retardation at plasma levels that were 2 times the human serum levels.
Embryonic loss has been seen in monkeys and rabbits (see TOXICOLOGY, Reproduction and Teratology).
AMOXICILLIN (amoxicillin trihydrate) Capsules
The safety of amoxicillin in the treatment of infections during pregnancy has not been established. If the administration of amoxicillin to pregnant patients is considered to be necessary, its use requires that the potential benefits be weighed against the possible hazards to the fetus.
Nursing Women
PREVACID® (lansoprazole delayed-release capsules)
Lansoprazole or its metabolites are excreted in the milk of rats. It is not known whether lansoprazole is excreted in human milk. As many drugs are excreted in human milk, lansoprazole should not be given to nursing mothers unless its use is considered essential. In this case nursing should be avoided.
BIAXIN BID® (clarithromycin tablets, USP, film-coated)
The safety of clarithromycin for use during breast-feeding of infants has not been established. Clarithromycin is excreted in human milk.
Preweaned rats, exposed indirectly via consumption of milk from dams treated with 150 mg/kg/day for 3 weeks, were not adversely affected, despite data indicating higher drug levels in milk than in plasma.
Pediatrics (1 to 17 years of age)
Hp-PAC® Triple Therapy: PREVACID®/clarithromycin/amoxicillin
The safety and effectiveness of Hp-PAC® in pediatric patients infected with H. pylori have not been established.
PREVACID® (lansoprazole delayed-release capsules)
Developmental toxicity studies revealed that exposure to lansoprazole in juvenile rats starting at postnatal Days 7, 14, and 21 (approximately equivalent to neonatal, 1, and 2 year old human, respectively) resulted in development of heart valve thickening (see TOXICOLOGY, Juvenile Animal Toxicity Data). However, the development of heart valve thickening has not been reported in pediatric clinical trials or in post-market reports.
Geriatrics
Hp-PAC® Triple Therapy: PREVACID®/clarithromycin/amoxicillin
Elderly patients may suffer from asympomatic renal and hepatic dysfunction. Care should be taken when administering Hp-PAC® to this patient population (see WARNINGS AND PRECAUTIONS, Hepatic/Biliary/Pancreatic and Renal).
PREVACID® (lansoprazole delayed-release capsules)
Benefits of use of PPIs should be weighed against the increased risk of fractures as patients in this category (> 71 years of age) may already be at high risk for osteoporosis-related fractures. If the use of PPIs is required, they should be managed carefully according to established treatment guidelines (see DOSAGE AND ADMINISTRATION and ADVERSE REACTIONS).
Ulcer healing rates in elderly patients are similar to those in younger age groups. The incidence rates of adverse events and laboratory test abnormalities are also similar to those seen in other age groups. The initial dosing regimen need not be altered for elderly patients, but subsequent doses higher than 30 mg / day should not be administered unless additional gastric acid suppression is necessary.
BIAXIN BID® (clarithromycin tablets, USP, film-coated)
Dosage adjustment should be considered in elderly patients with severe renal impairment. In a steady-state study in which healthy elderly subjects (age 65 to 81 years old) were given 500 mg every 12 hours, the maximum concentrations of clarithromycin and 14-OH clarithromycin were increased. The AUC was also increased. These changes in pharmacokinetics parallel known age-
related decreases in renal function. In clinical trials, elderly patients did not have an increased incidence of adverse events when compared to younger patients.
AMOXICILLIN (amoxicillin trihydrate) Capsules
Amoxicillin is known to be substantially excreted by the kidney, and the risk of toxic reactions to this drug may be greater in patients with impaired renal function. Because elderly patients are more likely to have decreased renal function, care should be taken in dose selection, and it may be useful to monitor renal function.
Monitoring and Laboratory Tests
Periodic assessment of renal, hepatic, and hematopoietic function should be made during prolonged therapy with amoxicillin.
ADVERSE REACTIONS
Adverse Drug Reaction Overview
Hp-PAC® Triple Therapy: PREVACID®/clarithromycin/amoxicillin
The most frequently reported (≥ 3%) adverse events for patients who received triple therapy were diarrhea (7%), headache (6%), and taste perversion (5%).
PREVACID® (lansoprazole delayed-release capsules)
Worldwide, over 10,000 patients have been treated with PREVACID® (lansoprazole) Delayed-Release Capsules during Phase II-III short-term and long-term clinical trials involving various dosages and duration of treatment. In general, lansoprazole treatment has been well tolerated.
BIAXIN BID® (clarithromycin tablets, USP, film-coated)
The majority of side effects observed in clinical trials involving 3563 patients treated with BIAXIN BID® were of a mild and transient nature. Fewer than 3% of adult patients without mycobacterial infections discontinued therapy because of drug-related side-effects. The most common drug-related adverse reactions in adults taking BIAXIN BID® were nausea, diarrhea, abdominal pain, dyspepsia, headache, taste perversion and vomiting.
Clinical Trial Adverse Drug Reactions
Because clinical trials are conducted under very specific conditions the adverse reaction rates observed in the clinical trials may not reflect the rates observed in practice and should not be compared to the rates in the clinical trials of another drug. Adverse drug reaction information from clinical trials is useful for identifying drug-related adverse events and for approximating rates.
Hp-PAC® Triple Therapy: PREVACID®/clarithromycin/amoxicillin
Patients in the 7-day triple therapy regimen reported fewer adverse events than those in the 10- and/or 14-day triple therapy regimens. There were no statistically significant differences in the frequency of reported adverse events between the 10- and 14-day triple therapy regimens. No treatment-emergent adverse events were observed at significantly higher rates with triple therapy than with any dual therapy regimen.
Combination Therapy with Clarithromycin and Amoxicillin
In clinical trials using combination therapy with PREVACID® plus clarithromycin and amoxicillin, no adverse reactions related to these drug combinations were observed. Adverse reactions that have occurred have been limited to those that have been previously reported with PREVACID®, clarithromycin, or amoxicillin.
For more information on adverse reactions with lansoprazole, clarithromycin or amoxicillin, refer to their respective Product Monographs, under the ADVERSE REACTIONS section.
PREVACID® (lansoprazole delayed-release capsules)
The following adverse events were reported to have a possible or probable relationship to drug as described by the treating physician in 1% or more of lansoprazole delayed-release capsules-treated patients who participated in placebo- and positive-controlled trials (Table 2 and Table 3, respectively). Numbers in parentheses indicate the percentage of the adverse events reported.
Table 2. Incidence of Possibly or Probably Treatment-Related Adverse Events in Short-Term,
Placebo-Controlled Studies in Takeda* Safety Database
Body System/Adverse Event† PREVACID®‡
(N = 817) N (%)
Placebo (N = 254) N (%)
Body as a Whole
Headache 63 (7.7) 31 (12.2)
Abdominal Pain 19 (2.3) 3 (1.2)
Digestive System
Diarrhea 29 (3.5) 6 (2.4)
Nausea 9 (1.1) 5 (2.0)
Vomiting 7 (0.9) 3 (1.2)
Liver Function Tests Abnormal 2 (0.2) 3 (1.2)
Nervous System
Dizziness 8 (1.0) 2 (0.8)
* Takeda Pharmaceuticals America Inc.
† Events reported by at least 1% of patients on either treatment are included
‡ Doses 15, 30 and 60 mg once daily for 4 to 8 weeks
In the Takeda Safety Database, all short-term, Phase II/III studies, 1 or more treatment-emergent adverse events were reported by 715/1359 (52.6%) PREVACID®-treated patients; of those considered to be possibly or probably treatment-related adverse events, 1 or more were reported by 276/1359 (20.3%) PREVACID®-treated patients. In all short-term, Phase II/III studies, 1 or more treatment-emergent adverse events were reported by 150/254 (59.1%) placebo-treated patients; of those considered to be possibly or probably treatment-related adverse events, 1 or more were reported by 56/254 (22.0%).
The most frequent adverse events reported in the European short-term studies were diarrhea (3.3%), laboratory test abnormal (2.3%), headache (1.5%), constipation (1.2%), asthenia (1.1%), dizziness (1.1%), and abdominal pain (1.0%). The most frequent adverse events reported in the Asian short-term studies were unspecified laboratory test abnormalities (7.3%), eosinophilia (1.0%), and increased SGPT (1.0%).
Table 3. Incidence of Possibly or Probably Treatment-Related Adverse Events in Short-Term,
Positive-Controlled Studies in Takeda† Safety Database
Body System/Adverse Event* PREVACID®‡
(N = 647) N (%)
Ranitidine (N = 393) N (%)
Body as a Whole
Headache 26 (4.0) 14 (3.6)
Abdominal Pain 8 (1.2) 3 (0.8)
Digestive System
Diarrhea 27 (4.2) 8 (2.0)
Nausea 7 (1.1) 4 (1.0)
Nervous System
Dizziness 8 (1.2) 3 (0.8)
Skin and Appendages/
Rash 7 (1.1) 1 (0.3)
† Takeda Pharmaceuticals America, Inc
* Events reported by at least 1% of patients on either treatment are included
‡ Doses 15, 30 and 60 mg once daily for 4 to 8 weeks
Less Common Clinical Trial Adverse Drug Reactions
Hp-PAC® Triple Therapy: PREVACID®/clarithromycin/amoxicillin
The additional adverse reactions which were reported as possibly or probably related to treatment (< 3%) in clinical trials when all 3 components of this therapy were given concomitantly are listed below and divided by body system:
Body as a Whole: abdominal pain
Digestive System: dark stools, dry mouth/thirst, glossitis, rectal itching, nausea, oral moniliasis, stomatitis, tongue discoloration, tongue disorder, vomiting
Musculoskeletal
System:
myalgia
Nervous System: confusion, dizziness
Respiratory System: respiratory disorders
Skin and Appendages: skin reactions
Urogenital System: vaginitis, vaginal moniliasis
PREVACID® (lansoprazole delayed-release capsules)
Additional adverse experiences occurring in < 1% of patients or subjects in domestic and/or international trials, or occurring since the drug was marketed, are shown below within each body system. Other adverse reactions have been observed during post-marketing surveillance; see (Post-Market Adverse Drug Reactions).
Body as a Whole: abdomen enlarged, allergic reaction, asthenia, candidiasis, carcinoma, chest pain (not otherwise specified), chills, edema, fever, flu syndrome, general pain, halitosis, infection (not otherwise specified), malaise, neck pain, neck rigidity, pelvic pain
Cardiovascular System: angina, arrhythmia, bradycardia, cerebrovascular accident/cerebral infarction, hypertension/hypotension, migraine, myocardial infarction, palpitations, shock (circulatory failure), syncope, tachycardia, vasodilation
Digestive System: abnormal stools, anorexia, bezoar, carcinoid, cardiospasm,
cholelithiasis, colitis, constipation, dry mouth, dyspepsia, dysphagia, enteritis, eructation, esophageal stenosis, esophageal ulcer, esophagitis, fecal discoloration, flatulence, gastric nodules/fundic gland polyps, gastroenteritis, gastrointestinal disorder, gastrointestinal hemorrhage, glossitis, gum hemorrhage, hematemesis, increased appetite, increased salivation, melena, mouth ulceration, oral monoliasis, rectal disorder, rectal hemorrhage, stomatitis, tenesmus, thirst, tongue disorder, ulcerative colitis, ulcerative stomatitis
Endocrine System: diabetes mellitus, goiter, hypothyroidism
Hemic and
Lymphatic System*:
anemia, hemolysis, lymphadenopathy
Metabolism and Nutritional
Disorders:
dehydration, gout, hyperglycemia/hypoglycemia, peripheral edema, weight gain/loss
Musculoskeletal System: arthralgia, arthritis, bone disorder, joint disorder, leg cramps, musculoskeletal pain, myalgia, myasthenia, synovitis
Nervous System: abnormal dreams, agitation, amnesia, anxiety, apathy, confusion, convulsion, depersonalization, depression, diplopia, dizziness, emotional lability, hallucinations, hemiplegia, hostility aggravated, hyperkinesia, hypertonia, hypesthesia, insomnia, libido decreased, libido increased, nervousness, neurosis, paresthesia, sleep disorder, somnolence, thinking abnormality, tremor, vertigo
Respiratory System: asthma, bronchitis, cough increased, dyspnea, epistaxis, hemoptysis, hiccup, laryngeal neoplasia, pleural disorder, pneumonia, stridor, upper respiratory inflammation/infection
Skin and Appendages: acne, alopecia, contact dermatitis, dry skin, fixed eruption, hair disorder, maculopapular rash, nail disorder, pruritus, rash, skin carcinoma, skin disorder, sweating, urticaria
Special Senses: abnormal vision, blurred vision, conjunctivitis, deafness, dry eyes, ear disorder, eye pain, ophthalmologic disorders, otitis media, parosmia, photophobia, retinal degeneration, taste loss, taste perversion, tinnitus, visual field defect
Urogenital System: abnormal menses, breast enlargement, breast tenderness, dysmenorrhea, dysuria, gynecomastia, impotence, kidney calculus, kidney pain, leukorrhea, menorrhagia, menstrual disorder, penis disorder, polyuria, testis disorder, urethral pain, urinary frequency, urination impaired, urinary urgency, vaginitis
* The majority of hematologic cases received were foreign-sourced and their relationship to lansoprazole was unclear.
BIAXIN BID® (clarithromycin tablets, USP, film-coated)
The following adverse reactions from the Clarithromycin Product Monograph, reported during clinical trials and during post-marketing surveillance, are provided for information:
Body as a Whole: asthenia, back pain, chest pain, headache (2%), infection, pain
Cardiovascular System: As with other macrolides, QT prolongation, ventricular tachycardia, and torsades de pointes have rarely been reported with clarithromycin.
Digestive System: abdominal pain (2%), anorexia, constipation, diarrhea (3%), dry mouth, dyspepsia (2%), flatulence, gastrointestinal disorder, glossitis, hepatomegaly, nausea (4%), oral moniliasis, pseudomembranous colitis, stomatitis, tongue discoloration, vomiting (1%). There have been reports of tooth discoloration in patients treated with BIAXIN BID®. Tooth discoloration is usually reversible with professional dental cleaning.
As with other macrolides, hepatic dysfunction, including increased liver enzymes, and hepatocellular and/or cholestatic hepatitis, with or without jaundice, has been infrequently reported with BIAXIN BID®. This hepatic dysfunction may be severe and is usually reversible. In very rare instances, hepatic failure with fatal outcome has been reported and generally has been associated with serious underlying diseases and/or concomitant medications.
Metabolic: There have been rare reports of hypoglycemia, some of which have occurred in patients on concomitant oral hypoglycemic agents or insulin.
Nervous System: anxiety, confusion, depersonalization, depression, disorientation, dizziness, hallucinations, insomnia, nervousness, nightmares, psychosis, somnolence, tinnitus, vertigo. Central nervous system side effects (including seizures) have been occasionally reported with erythromycin, another macrolide.
Respiratory System: asthma, cough increased, dyspnea, pharyngitis, rhinitis
Skin and Appendages: pruritus, rash, sweating; allergic reactions ranging from urticaria and mild skin eruptions to anaphylaxis and Stevens-Johnson Syndrome have occurred with orally administered clarithromycin.
Special Senses: abnormal vision, conjunctivitis, ear disorder, taste perversion (2%).
There have been reports of hearing loss with clarithromycin which is usually reversible upon withdrawal of therapy. Reports of alteration of the sense of smell, usually in conjunction with taste perversion or taste loss have also been reported.
Urogenital System: dysmenorrhea, hematuria, vaginal moniliasis, vaginitis
Hemic and
Lymphatic System:
anemia, eosinophilia, leukopenia, thrombocythemia. Isolated cases of thrombocytopenia have been reported.
Other: In studies of adults with pneumonia comparing clarithromycin to erythromycin base or erythromycin stearate, there were significantly fewer adverse events involving the digestive system in patients treated with clarithromycin.
AMOXICILLIN (amoxicillin trihydrate) Capsules
As with other penicillins, it may be expected that untoward reactions will be related to sensitivity phenomena. They are more likely to occur in individuals who have previously demonstrated hypersensitivity to penicillins and cephalosporins and in those with a history of allergy, asthma, hay fever or urticaria.
The following adverse reactions have been reported as associated with the use of amoxicillin.
Gastrointestinal: nausea, vomiting and diarrhea, hemorrhagic and pseudomembranous colitis. Clostridium difficile-associated disease (CDAD) has been reported with use of many antibacterial agents, including amoxicillin. Glossitis, black “hairy” tongue and stomatitis, mucocutaneous candidiasis, tooth discoloration (brown, yellow or gray staining); most reports occurred in pediatric patients. Discoloration was reduced or eliminated with brushing or dental cleaning in most cases.
Hypersensitivity Reactions:
Skin rashes have been reported frequently. Less commonly, a few cases of serum sickness like reactions including urticaria, erythema, erythema multiforme, angioneurotic edema, pruritus have been reported. Rarely, Stevens-Johnson syndrome, toxic epidermal necrolysis, bullous dermatitis, exfoliative dermatitis, acute generalized exanthematous pustulosis, hypersensitivity vasculitis have been reported.
Anaphylaxis is the most serious reaction experienced and has usually been associated with the parenteral dosage form.
Note: Urticaria, other skin rashes, and serum sickness–like reactions may be controlled with antihistamines and if necessary, systemic corticosteroids. Whenever such reactions occur, Amoxicillin (amoxicillin trihydrate) should be discontinued unless, in the opinion of the physician, the condition being treated is life threatening and amenable only to amoxicillin therapy. Serious anaphylactic reactions require the immediate use of epinephrine, oxygen and intravenous steroids.
Hepatobiliary: A moderate rise in serum glutamic oxaloacetic transaminase (SGOT)
has been noted, particularly in infants, but the significance of this finding is not known. Transient increases in serum alkaline phosphatase and lactic dehydrogenase levels have also been observed but they returned to normal on discontinuation of amoxicillin. Reports have also been seen of hepatic dysfunction including cholestatic jaundice, hepatic cholestasis, and acute cytolytic hepatitis.
Hemic and
Lymphatic Systems:
anemia thrombocytopenia, thrombocytopenic purpura, eosinophilia, leukopenia, neutropenia and agranulocytosis have been reported during therapy with the penicillins. These reactions are usually reversible on discontinuation of therapy and are believed to be a hypersensitivity phenomena. Reports have also been seen of anemia including hemolytic anemia.
Central Nervous System: As with other penicillins, acute and chronic toxicity is not a clinical problem. Although penicillins do not normally cross the blood-brain barrier to any substantial extent, if massive doses are given (several grams per day) to elderly patients, patients with inflamed meninges or patients with impaired renal function, toxic reactions are likely to occur. At extremely high doses, convulsions can occur. When penicillin reaches a high concentration in the cerebrospinal fluid, neurotoxic symptoms consisting of myoclonia, convulsive seizures and depressed consciousness may occur. Unless administration of the drug is stopped or its dosage reduced, the syndrome may progress to coma and death. Dizziness, hyperkinesias, hyperactivity, agitation, anxiety, insomnia, confusion and behavioural changes have also been reported.
Skin and appendages: Erythematous maculopapular rash.
Renal: Crystalluria. Interstitial nephritis (oliguria, proteinuria, hematuria, hyaline casts, pyuria) and nephropathy are infrequent and usually associated with high doses of parenteral penicillins; however, this has occurred with all of the penicillins. Such reactions are hypersensitivity responses and are usually associated with fever, skin rash and eosinophilia. Elevations of creatinine or blood urea nitrogen may occur.
Abnormal Hematologic and Clinical Chemistry Findings
PREVACID® (lansoprazole delayed-release capsules)
In addition, the following changes in laboratory parameters were reported as adverse events. Abnormal liver function tests, increased SGOT (AST), increased SGPT (ALT), increased creatinine, increased alkaline phosphatase, increased gamma globulins, increased GGTP, increased/decreased/abnormal white blood cells (WBC), abnormal AG ratio, abnormal red blood cells (RBC), bilirubinemia, eosinophilia, hyperlipemia, increased/decreased electrolytes, increased/decreased cholesterol, increased glucocorticoids, increased lactate dehydrogenase (LDH), increased/decreased/abnormal platelets, and increased gastrin levels. Urine abnormalities such as albuminuria, glycosuria, and hematuria were also reported. Additional isolated laboratory abnormalities were reported.
In the placebo controlled studies, when SGOT (AST) and SGPT (ALT) were evaluated, 0.4% (4/978) and 0.4% (11/2677) patients, who received placebo and lansoprazole, respectively had
enzyme elevations > 3 x upper limit of normal range at the final treatment visit. None of these lansoprazole patients reported jaundice at any time during the study.
For more information on laboratory value changes with amoxicillin, refer to the respective Product Monograph, under the ADVERSE REACTIONS section.
BIAXIN BID® (clarithromycin tablets, USP, film-coated)
Changes in laboratory values with possible clinical significance reported during clinical studies or during post-marketing surveillance are displayed in Table 4.
Table 4. Abnormal Hematologic and Clinical Chemistry Findings in Patients with Respiratory Tract or Skin Infections Treated with BIAXIN BID®
System Organ Class | Laboratory Values | Frequency |
| Investigations | Alanine aminotransferase increased Aspartate aminotransferase increased Gamma-glutamyltransferase increased Blood alkaline phosphatase increased Blood lactate dehydrogenase increased Blood bilirubin increased Blood creatinine increased White blood cell count decreased | Uncommon (Less than 1%) |
Prothrombin time prolonged Blood urea increased | 1% 4% |
Post-Market Adverse Drug Reactions
PREVACID® (lansoprazole delayed-release capsules)
These events were reported during post-marketing surveillance. Estimates of frequency cannot be made since such events are reported voluntarily from a population of unknown size. Due to the uncontrolled nature of spontaneous reports, a clear causal relationship to lansoprazole cannot be established.
Body as a Whole: hypersensitivity reactions, including anaphylaxis
Digestive System: colitis, hepatotoxicity, pancreatitis, vomiting
Hemic and
Lymphatic System:
agranulocytosis, aplastic anemia, hemolytic anemia, leukopenia, neutropenia, pancytopenia, thrombocytopenia, thrombotic thrombocytopenic purpura
Metabolism and Nutritional
Disorders:
hypomagnesemia
Musculoskeletal System: myositis, osteoporosis and osteoporosis-related fractures
Skin and Appendages: severe dermatologic reactions including cutaneous lupus erythematosus, erythema multiforme, Stevens-Johnson Syndrome, toxic epidermal necrolysis (some fatal)
Special Senses: speech disorder
Urogenital System: interstitial nephritis (with possible progression to renal failure), urinary retention
In an estimated exposure of 240 million patients worldwide (in both postmarketing surveillance and the clinical trials), the most commonly reported ophthalmic adverse events are amblyopia (13) and vision blurred (67) according to the MedDRA terminology. All the 13 cases of amblyopia had the reported term/verbatim “blurred or smeary vision”. Only 2 of these 13 reports were considered serious, and both are foreign-sourced reports with very little information provided. Among the 67 reports with the “vision blurred”, 10 were considered serious and might be related to optic neuritis/neuropathy, whether or not believed related to the drug. In 2 of these 10 cases, 1 of the examining ophthalmologists proposed a diagnosis of anerior-ischemic optic neurpathy (AION). Eight out of the 10 cases were foreign-sourced. Only 2 US-sourced serious cases involved the report of blurred vision. Both were consumer reports without any detailed information. No physician assessed any causality in either case.
Withdrawal of long term PPI therapy can lead to aggravation of acid related symptoms and may result in Rebound Acid Hyper-secretion.
There have been post-marketing reports of subacute cutaneous lupus erythematosus (SCLE) (See WARNINGS AND PRECAUTIONS, Immune).
BIAXIN BID® (clarithromycin tablets, USP, film-coated)
The following list of adverse events is a compilation of adverse reactions from Postmarketing Surveillance and Postmarketing Clinical Studies for all clarithromycin formulations.
Table 5. Clarithromycin Post-Market Adverse Drug Reactions
System Organ Class Adverse Event
Blood and lymphatic system disorders Agranulocytosis, leukopenia, thrombocytopenia
Cardiac disorders1 Atrial fibrillation, cardiac arrest, electrocardiogram QT prolonged, extrasystoles, palpitations, torsades de pointes, ventricular tachycardia
Ear and labyrinth disorders Deafness, hearing impaired, hearing loss2, tinnitus, vertigo
Gastrointestinal disorders Abdominal pain, constipation, dry mouth, dyspepsia, eructation, esophagitis, flatulence, gastritis, glossitis, pancreatitis, stomatitis, tongue discoloration, tooth discoloration, vomiting
General disorders and administration site conditions Asthenia
Hepatobiliary disorders Hepatic function abnormal, hepatitis, hepatitis
cholestatis, hepatic failure3, jaundice (cholestatic and hepatocellular)
Immune system disorders Angioedema, anaphylactic reaction, anaphylactoid reaction, anaphylaxis, hypersensitivity, myasthenia gravis
Infections and infestations Candidiasis, cellulitis, pseudomembranous colitis, vaginal infection
Investigations Albumin globulin ratio abnormal, alanine
aminotransferase increased, aspartate aminotransferase increased, blood creatinine increased, blood urea increased, international normalized ratio (INR) increased4, liver enzymes increased, liver function tests abnormal, prothrombin time prolonged4, urine color abnormal5
Metabolism and nutrition disorders Anorexia, decreased appetite
Musculoskeletal and connective tissue disorders Musculoskeletal stiffness, myalgia, myopathy,
rhabdomyolysis6
Nervous system disorders Aguesia, alteration of sense of smell, anosmia,
convulsions, dizziness, dysgeusia, dyskinesia, headache, loss of consciousness, paraesthesia, parosmia, tremor, somnolence
Psychiatric disorders Abnormal dreams, anxiety, bad dreams, confusion, depersonalization, depression, disorientation, hallucination, insomnia, mania, psychosis
Renal and urinary disorders Interstitial nephritis, renal failure
System Organ Class Adverse Event
Respiratory, thoracic and mediastinal disorders Asthma, pulmonary embolism
Skin and subcutaneous tissue disorders Acne, dermatitis bullous, drug rash with eosinophilia and systemic symptoms (DRESS), Henoch-Schonlein purpura, hyperhidrosis, pruritus, rash, mild skin eruptions, Stevens Johnson syndrome, toxic epidermal necrolysis, urticaria
Vascular disorders Hemorrhage4, vasodilation
1 As with other macrolides, QT prolongation, ventricular tachycardia, and torsades de pointes have been reported with clarithromycin.
2 There have been reports of hearing loss with clarithromycin which is usually reversible upon withdrawal of therapy. 3 Hepatic dysfunction may be severe and is usually reversible. Hepatic failure with fatal outcome has been reported and generally has been associated with serious underlying diseases and/or concomitant medications. 4 When clarithromycin is co-administered with warfarin.
5 Symptom of hepatic failure.
6 In some of the reports of rhabdomyolysis, clarithromycin was administered concomitantly with other drugs known to be associated with rhabdomyolosis (such as statins, fibrates, colchicine or allopurinol).
Colchicine
There have been post-marketing reports of colchicine toxicity with concomitant use of clarithromycin and colchicine, especially in the elderly, some of which occurred in patients with renal insufficiency. Deaths have been reported in some such patients (see CONTRAINDICATIONS).
DRUG INTERACTIONS
Serious Drug Interactions
Concomitant administration of clarithromycin with astemizole, cisapride, colchicine, pimozide, terfenadine, lovastatin, simvastatin, ergot alkaloids (e.g., ergotamine, dihydroergotamine), saquinavir/ritonavir is contraindicated
(see CONTRAINDICATIONS and DRUG INTERACTIONS).
Clarithromycin is an inhibitor of the cytochrome P450 3A isoform subfamily (CYP3A)
and the P-glycoprotein transporter (P-gp). The concomitant administration of clarithromycin and drugs metabolized by CYP3A and/or transported by P-gp may lead to an increase in the plasma concentrations of the co-administered drug which could result in clinically significant safety concerns.
Overview
PREVACID® (lansoprazole delayed-release capsules)
Lansoprazole is metabolized through the cytochrome P450 system, specifically through CYP3A and CYP2C19. Studies have shown that lansoprazole does not have clinically significant interactions with other drugs metabolized by the cytochrome P450 system such as warfarin, antipyrine, indomethacin, acetylsalicylic acid, ibuprofen, phenytoin, prednisone, diazepam, clarithromycin, propranolol, amoxicillin or terfenadine in healthy subjects. These compounds are metabolized through various cytochrome P450 isozymes including CYP1A2, CYP2C9, CYP2C19, CYP2D6, and CYP3A.
Drugs that Inhibit or Induce CYP2C19
Inhibitors of CYP2C19 such as fluvoxamine would likely increase the systemic exposure of lansoprazole. Inducers of CYP2C19 may decrease the systemic exposure of lansoprazole.
Drugs with pH Dependent Absorption Pharmacokinetics
Lansoprazole causes a profound and long lasting inhibition of gastric acid secretion; therefore, lansoprazole may interfere with the absorption of drugs where gastric pH is an important determinant of bioavailability (e.g., ketoconazole, ampicillin esters, iron salts, digoxin).
BIAXIN BID® (clarithromycin tablets, USP, film-coated)
Many categories of drugs are metabolized by CYP3A and/or transported by P-gp located in the liver and in the intestine. Some drugs inhibit and others induce the activities of CYP3A and/or P-gp. Administration of such inhibitors or inducers may impact upon the metabolism. In some cases serum concentration may be increased and in others decreased. Care must therefore be exercised when co-administering such drugs.
Clarithromycin is reported to be an inhibitor of CYP3A and P-gp. This may lead to increased or prolonged serum levels of those drugs also metabolized by CYP3A or transported by P-gp when co-administered with clarithromycin. For such drugs the monitoring of their serum concentrations may be necessary.
Clarithromycin should be used with caution in patients receiving treatment with other drugs known to be CYP3A and/or P-gp substrates, especially if the CYP3A/P-gp substrate has a narrow safety margin (e.g., carbamazepine) and/or the substrate is extensively metabolized by CYP3A or transported by P-gp. Dosage adjustments may be considered, and when possible, serum concentrations of these drugs should be monitored closely in patients concurrently receiving clarithromycin.
With certain drugs, co-administration of clarithromycin is contraindicated or should be avoided (see Table 7).
Drug-Drug Interactions.
PREVACID® (lansoprazole delayed-release capsules)
Table 6 summarizes the established and potential drug interactions with PREVACID®.
Table 6. Established or Potential Drug-Drug Interactions with PREVACID®
Concomitant Drug
Name
| Ref | Effect |
Clinical Comment
Antiretroviral Drugs
| C | ↓ rilpivirine, atazanavir, nelfinavir ↑saquinavir |
Rilpivirine
Co-administration is contraindicated due to significant decrease in exposure and loss of therapeutic effect (see CONTRAINDICATIONS).
Atazanavir
Co-administration of Hp-PAC® with atazanavir is not recommended. Concomitant administration of omeprazole (20 or 40 mg once daily) substantially reduced plasma Cmax and AUC of atazanavir in healthy volunteers administered atazanavir or
atazanavir/ritonavir. (see REYATAZ® Product Monograph).
Nelfinavir
Co-administration of Hp-PAC® with nelfinavir is not recommended. Concomitant administration of omeprazole (40 mg daily) with nelfinavir (1250 mg twice daily) markedly reduced the AUC and Cmax for nelfinavir (by 36% and 37%, respectively) and its active metabolite M8 (by 92% and 89%, respectively) (see VIRACEPT® Product Monograph).
Saquinavir
Co-administration of saquinavir requires caution and monitoring, along with potential dose reduction of saquinavir, due to increased saquinavir exposure and thus the risk of saquinavir-related toxicities (see the INVIRASE® Product Monograph).
Concomitant administration of omeprazole (40 mg daily) with saquinavir/ritonavir (1000/100 mg twice daily) increased saquinavir AUC by 82% and Cmax by 75%.
Clopidogrel
| CT | - |
Concomitant administration of lansoprazole and clopidogrel in healthy subjects had no clinically important effect on exposure to the active metabolite of clopidogrel or clopidogrel-induced platelet inhibition. No dose adjustment of clopidogrel is necessary when administered with an approved dose of lansoprazole.
Concomitant Drug Name
| Ref | Effect |
Clinical Comment
CYP450
Methotrexate
| C, CT | - |
Case reports, published population pharmacokinetic studies, and retrospective analyses suggest that concomitant administration of PPIs and methotrexate (primarily at high dose) may elevate and prolong serum levels of methotrexate and/or its metabolite hydroxymethotrexate, possibly leading to methotrexate toxicities. However, no formal drug interaction studies of high dose methotrexate with PPIs have been conducted.
In an open-label, single-arm, eight day, pharmacokinetic study of 28 adult rheumatoid arthritis patients (who required the chronic use of 7.5 to 15 mg of methotrexate given weekly), administration of 7 days of naproxen 500 mg twice daily and PREVACID® 30 mg daily had no effect on the pharmacokinetics of methrotrexate and 7-hydroxymethotrexate. While this study was not designed to assess the safety of this combination of drugs, no major adverse reactions were noted. However, this study was conducted with low doses of methotrexate. A drug interaction study with high doses of methotrexate has not been conducted.
Sucralfate
| CT | Lansoprazole: AUC ↓, Cmax ↓ |
Proton pump inhibitors should be taken at least 30 minutes prior to sucralfate. In clinical trials, antacids were administed with lansoprazole and there was no evidence of a change in the efficacy of lansoprazole (see ACTION AND CLINICAL
PHARMACOLOGY, Pharmacokinetics, Absorption, Absorption with Antacids).
Tacrolimus
| C | Increased whole blood levels |
Concomitant administration of PREVACID® and tacrolimus may increase whole blood levels of tacrolimus, especially in transplant patients who are intermediate or poor metabolizers of CYP2C19.
Theophylline
(CYP1A2, CYP3A)
| CT | 10% increase in theophylline clearance |
Minor increase of theophylline clearance is unlikely to be of clinical concern.
Individual patients may require adjustment of their theophylline dosage when PREVACID® is started or stopped to ensure clinically effective blood levels.
Patient monitoring should be taken in coadministration of lansoprazole with theophylline.
Concomitant Drug Name
| Ref | Effect |
Clinical Comment
Warfarin
| C, CT | ↑ INR and PT |
In a study of healthy subjects, neither the
pharmacokinetics of warfarin enantiomers nor prothrombin time were affected following co-administration of single or multiple 60 mg doses of lansoprazole and warfarin; however, there have been reports of increased INR and prothrombin time in patients receiving proton pump inhibitors, including lansoprazole, and warfarin concomitantly. Increases in INR and prothrombin time may lead to abnormal bleeding and even death. Patients treated with proton pump inhibitors and warfarin concomitantly may need to be monitored for increases in INR and prothrombin time.
Legend: C = Case Study; CT = Clinical Trial; T = Theoretical
BIAXIN BID® (clarithromycin tablets, USP, film-coated)
Some of the drug-drug interactions which have been reported between clarithromycin-macrolides and other drugs or drug categories are listed in Table 7.
The drugs listed in Table 7 are based on drug interactions case reports, clinical trials, or potential interactions due to the expected mechanism of the interaction.
Table 7. Established or Potential Drug-Drug Interactions with Clarithromycin
Concomitant Drug
Name
| Ref. | Effect |
Clinical Comments
Astemizole* / Terfenadine
| CT | terfenadine-acid metabolite concentrations increase ↑ QT interval |
Macrolides have been reported to alter the metabolism of terfenadine resulting in increased serum levels of terfenadine which has occasionally been associated with cardiac arrhythmias such as QT prolongation, ventricular tachycardia, ventricular fibrillation and torsades de pointes (see CONTRAINDICATIONS).
In a study involving 14 healthy volunteers, the concomitant administration of BIAXIN BID® tablets and terfenadine resulted in a 2- to 3-fold increase in the serum levels of the acid metabolite of terfenadine, MDL 16, 455, and in prolongation of the QT interval. Similar effects have been observed with concomitant administration of astemizole and other macrolides.
Atazanavir
| CT | ↑ clarithromycin levels ↑ atazanavir AUC |
Both clarithromycin and atazanavir are substrates and inhibitors of CYP3A, and there is evidence of a bi-directional drug interaction. Co-administration of clarithromycin (500 mg twice daily) with atazanavir (400 mg once daily) resulted in a 2-fold increase in exposure to clarithromycin and a 70% decrease in exposure to 14-OH-clarithromycin, with a 28% increase in the AUC of atazanavir.
Because of the large therapeutic window for clarithromycin, no dosage reduction should be necessary in patients with normal renal function. For patients with moderate renal function (creatinine clearance 30 to 60 mL/min), the dose of clarithromycin should be decreased by 50%. For patients with creatinine clearance < 30 mL/min, the dose of clarithromycin should be decreased by 75% using an appropriate clarithromycin formulation. Doses of clarithromycin greater than 1000 mg per day should not be co-administered with protease inhibitors.
Calcium Channel Blockers
(e.g., verapamil, amlodipine,
diltiazem)
| C | Potential ↑ in verapamil concentrations |
Caution is advised regarding the concomitant administration of clarithromycin and calcium channel blockers metabolized by CYP3A4 (e.g., verapamil, amlodipine, diltiazem) due to the risk of hypotension. Plasma concentrations of clarithromycin as well as calcium channel blockers may increase due to the interaction. Hypotension, bradyarrhythmias, and lactic acidosis have been observed in patients receiving concurrent verapamil, belonging to the calcium channel blockers drug class.
Carbamazepine
| C | ↑ levels of carbamazepine |
Clarithromycin administration in patients receiving carbamazepine has been reported to cause increased levels of carbamazepine. Blood level monitoring of carbamazepine may be considered.
Concomitant Drug
Name
| Ref. | Effect |
Clinical Comments
Cisapride* / Pimozide
| C | ↑ levels of cisapride ↑ levels of pimozide |
Elevated cisapride levels have been reported in patients receiving clarithromycin and cisapride concomitantly. This may result in QT prolongation and cardiac arrhythmias including ventricular tachycardia, ventricular fibrillation and torsade de pointes. Similar effects have been observed in patients taking clarithromycin and pimozide concomitantly (see
CONTRAINDICATIONS).
Colchicine
| C | Potential colchicine toxicity |
Colchicine is a substrate for both CYP3A and the efflux transporter, P-glycoprotein (Pgp). Clarithromycin and other macrolides are known to inhibit CYP3A and Pgp. When clarithromycin and colchicine are administered together, inhibition of Pgp and/or CYP3A by clarithromycin may lead to increased exposure to colchicine. This risk may be further increased with concomitant medications metabolized by P-glycoprotein or strong CYP3A inhibitors. Concomitant use of clarithromycin and colchicine is contraindicated. See CONTRAINDICATIONS.
Cyclosporine
| C | ↑ levels of cyclosporine |
There have been reports of elevated cyclosporine serum concentrations when clarithromycin and cyclosporine are used concurrently. Cyclosporine levels should be monitored and the dosage should be adjusted as necessary. Patients should also be monitored for increased cyclosporine toxicity.
Didanosine
| CT | No change in didanosine pharmacokinentics in HIV-infected patients (n=12) |
Simultaneous administration of BIAXIN BID® tablets and didanosine to 12 HIV-infected adult patients resulted in no statistically significant change in didanosine pharmacokinetics.
Digoxin
| C | ↑ levels of digoxin |
Digoxin is thought to be a substrate for the efflux transporter, P-gp. Clarithromycin is known to inhibit P-gp. When clarithromycin and digoxin are administered together, inhibition of P-gp by clarithromycin may lead to increased exposure to digoxin.
Elevated digoxin serum concentrations have been reported in patients receiving BIAXIN BID® tablets and digoxin concomitantly.
In post-marketing surveillance some patients have shown clinical signs consistent with digoxin toxicity, including arrhythmias. Serum digoxin levels should be carefully monitored while patients are receiving digoxin and clarithromycin simultaneously.
Concomitant Drug
Name
| Ref. | Effect |
Clinical Comments
Disopyramide / Quinidine
| C | ↑ levels of disopyramide, resulting in ventricular fibrillation & QT prolongation (rarely reported) Torsades de pointes |
Increased disopyramide plasma levels, resulting in ventricular fibrillation and QT prolongation, coincident with the co-administration of disopyramide and clarithromycin have rarely been reported.
There have been post-marketing reports of torsades de pointes occurring with concurrent use of clarithromycin and quinidine or disopyramide. Electrocardiograms should be monitored for QTc prolongation during co-administration of clarithromycin with these drugs.
Serum levels of these medications should be monitored during clarithromycin therapy.
There have been post marketing reports of hypoglycemia with the concomitant administration of clarithromycin and disopyramide. Therefore blood glucose levels should be monitored during concomitant administration of clarithromycin and disopyramide.
Ergot alkaloids
Ergotamine /
Dihydroergotamine
| C | Potential ischemic reactions Potential ergot toxicity |
Post-marketing reports indicate that co-administration of clarithromycin with ergotamine or dihydroergotamine has been associated with acute ergot toxicity characterized by severe peripheral vasospasm, dysesthesia, and ischemia of the extremities and other tissues including the central nervous system. Concomitant administration of clarithromycin and ergot alkaloids is contraindicated. See CONTRAINDICATIONS.
Etravirine
| CT | ↓ clarithromycin ↑14-OH-clarithromycin |
Clarithromycin exposure was decreased by etravirine; however, concentrations of the active metabolite, 14-OH-clarithromycin, were increased. Because 14-OH-clarithromycin has reduced activity against Mycobacterium avium complex (MAC), overall acitivity against this pathogen may be altered; therefore alternatives to clarithromycin should be considered for the treatment of MAC.
Fluconazole
| CT | ↑ clarithromycin Cmin & AUC |
Concomitant administration of fluconazole 200 mg daily and clarithromycin 500 mg twice daily to 21 healthy volunteers led to increases in the mean steady-state clarithromycin Cmin and AUC of 33% and 18%, respectively.
Steady-state concentrations of 14-OH clarithromycin were not significantly affected by concomitant administration of fluconazole.
Concomitant Drug
Name
| Ref. | Effect |
Clinical Comments
HMG-CoA
Reductase Inhibitors
Lovastatin /
Simvastatin
| C | Rhabdomyolysis (rarely reported) |
Concomitant use of clarithromycin with lovastatin or simvastatin is contraindicated (see
CONTRAINDICATIONS) as these statins are extensively metabolized by CYP3A4 and concomitant treatment with clarithromycin increases their plasma concentration, which increases the risk of myopathy, including rhabdomyolysis. Reports of rhabdomyolysis have been received for patients taking clarithromycin concomitantly with these statins. If treatment with clarithromycin cannot be avoided, therapy with lovastatin or simvastatin must be suspended during the course of treatment.
Atorvastatin
Rosuvastatin
| C |
Rare reports of rhabdomyolysis have also been reported in patients taking atorvastatin or rosuvastatin concomitantly with clarithromycin. Concurrent use of atorvastatin and clarithromycin may result in increased atorvastatin exposure.
Caution should be exercised when prescribing clarithromycin with statins. In situations where the concomitant use of clarithromycin with statins cannot be avoided, it is recommended to prescribe the lowest registered dose of the statin. Use of a statin that is not dependent on CYP3A metabolism (e.g., fluvastatin) can be considered. Patients should be monitored for signs and symptoms of myopathy.
Itraconazole
| CT, P | ↑ levels of clarithromycin ↑ levels of itraconazole |
Both clarithromycin and itraconazole are substrates and inhibitors of CYP3A, leading to a bi-directional drug interaction. Clarithromycin may increase the plasma levels of itraconazole, while itraconazole may increase the plasma levels of clarithromycin. Patients taking itraconazole and clarithromycin concomitantly should be monitored closely for signs or symptoms of increased or prolonged pharmacologic effect.
Concomitant Drug
Name
| Ref. | Effect |
Clinical Comments
Lansoprazole / Omeprazole
| CT | Mild change of lansoprazole and 14-OH-clarithromycin concentrations ↑ omeprazole Cmax & AUC0-24 ↑ levels of clarithromycin |
One study demonstrated that concomitant administration of clarithromycin and lansoprazole resulted in mild changes of serum concentrations of lansoprazole and 14-OH clarithromycin. However, no dosage adjustment is considered necessary based on these data.
Clarithromycin 500 mg three times daily was given in combination with omeprazole 40 mg once daily to healthy subjects. The steady-state plasma concentrations of omeprazole were increased (i.e., Cmax, AUC0-24, and t½ increased by 30%, 89%, and 34%, respectively), by concomitant administration of clarithromycin. The mean 24-hour gastric pH value was 5.2 when omeprazole was administered alone and 5.7 when co-administered with clarithromycin.
To a lesser extent, omeprazole administration increases the serum concentrations of clarithromycin. Omeprazole administration also increases tissue and mucus concentrations of clarithromycin.
Oral Anticoagulants
Warfarin /
Acenocoumarol
| C | ↑ anticoagulant effect |
There have been reports of increased anticoagulant effect when clarithromycin and oral anticoagulants are used concurrently. Anticoagulant parameters should be closely monitored. Adjustment of the anticoagulant dose may be necessary.
Clarithromycin has also been reported to increase the anticoagulant effect of acenocoumarol.
There is a risk of serious hemorrhage and significant elevations in International Normalized Ratio (INR) and prothrombin time when clarithromycin is co-administered with warfarin. INR and prothrombin times should be frequently monitored while patients are receiving clarithromycin and oral anticoagulants concurrently.
Oral Hypoglycemic Agents
(e.g., Insulin)
C P | Hypoglycemia |
The concomitant use of clarithromycin and oral hypoglycaemic agents (such as sulphonylurias) and/or insulin can result in significant hypoglycaemia. With certain hypoglycaemic drugs such as nateglinide, pioglitazone, repaglinide and rosiglitazone, inhibition of CYP3A enzyme by clarithromycin may be involved and could cause hypoglycaemia when used concomitantly. Careful monitoring of glucose is recommended.
Concomitant Drug
Name
| Ref. | Effect |
Clinical Comments
Phosphodiesterase inhibitors
(e.g., sildenafil,
tadalafil , vardenafil)
| P | ↑ phosphodiesterase inhibitor exposure |
Sildenafil, tadalafil, and vardenafil are metabolized, at least in part, by CYP3A, and CYP3A may be inhibited by concomitantly administered clarithromycin. Co-administration of clarithromycin with sildenafil, tadalafil or vardenafil would likely result in increased phosphodiesterase inhibitor exposure. Reduction of sildenafil, tadalafil and vardenafil dosages should be considered when these drugs are co-administered with clarithromycin.
Rifabutin
| C | ↓ levels of clarithromycin ↑ levels of rifabutin |
Clarithromycin has been reported to increase serum and tissue concentration of rifabutin and thus may increase the risk of toxicity. Clarithromycin levels decrease when co-administered with rifabutin.
Concomitant administration of clarithromycin and rifabutin in the treatment of Mycobacterial Avium complex infections resulted in rifabutin-associated uveitis.
A case control study in AIDS patients showed that concomitant administration of rifabutin and clarithromycin resulted in an approximately 50% reduction in serum clarithromycin concentration, approximately 77% increase in the area under the plasma concentration-time curve of rifabutin, and a 236% increase in the area under the plasma concentration-time curve of rifabutin’s active metabolite. The increase in rifabutin and/or its metabolite contributed to the development of uveitis (the incidence of uveitis was 14% in patients weighing > 65 kg, 45% in patients between 55 and 65 kg, and 64% in patients < 55 kg).
Concomitant Drug
Name
| Ref. | Effect |
Clinical Comments
Ritonavir / Indinavir
| CT | ↑ clarithromycin Cmax, Cmin & AUC |
A pharmacokinetic study demonstrated that the concomitant administration of ritonavir 200 mg every 8 hours and clarithromycin 500 mg every 12 hours resulted in a marked inhibition of the metabolism of clarithromycin. The clarithromycin Cmax increased by 31%, Cmin increased 182% and AUC increased by 77% with concomitant administration of ritonavir. An essentially complete inhibition of the formation of 14-[R]-hydroxy-clarithromycin was noted. Because of the large therapeutic window for clarithromycin, no dosage reduction should be necessary in patients with normal renal function. However, for patients with renal impairment, the following dosage adjustments should be considered: For patients with creatinine clearance 30 to 60 mL/min the dose of clarithromycin should be reduced by 50%. For patients with creatinine clearance < 30 mL/min the dose of clarithromycin should be decreased by 75%. Doses of clarithromycin greater than 1 g/day should not be co-administered with ritonavir.
Similar dose adjustments should be considered in patients with reduced renal function when ritonavir is used as a pharmacokinetic enhancer with other HIV protease inhibitors including atazanavir and saquinavir.
↑ indinavir AUC ↑ clarithromycin AUC |
One study demonstrated that the concomitant administration of clarithromycin and indinavir resulted in a metabolic interaction; the clarithromycin AUC increased by 53% and the indinavir AUC was increased by 20%, but the individual variation was large. No dose adjustment is necessary with normal renal function.
Saquinavir/Ritonavir
Potentially life-threatening cardiac arrhythmia. Concomitant use of clarithromycin and saquinavir/ritonavir is contraindicated. See CONTRAINDICATIONS.
Concomitant Drug
Name
| Ref. | Effect |
Clinical Comments
Saquinavir
| CT | ↑ saquinavir AUC and Cmax ↑ clarithromycin AUC |
Both clarithromycin and saquinavir are substrates and inhibitors of CYP3A, and there is evidence of a bi-directional drug interaction.
Concomitant administration of clarithromycin (500 mg twice daily) and saquinavir (soft gelatin capsules, 1200 mg three times daily) to 12 healthy volunteers resulted in steady-state AUC and Cmax values of saquinavir which were 177% and 187% higher than those seen with saquinavir alone. Clarithromycin AUC and Cmax values were approximately 40% higher than those seen with clarithromycin alone.
No dose adjustment is required when the 2 drugs are co-administered for a limited time at the doses/ formulations studied.
Observations from drug interaction studies using the soft gelatin capsule formulation may not be representative of the effects seen using the saquinavir hard gelatin capsule. Observations from drug interaction studies performed with saquinavir alone may not be representative of the effects seen with saquinavir/ritonavir therapy. When saquinavir is co-administered with ritonavir, consideration should be given to the potential effects of ritonavir on clarithromycin.
Tacrolimus
| P | Potential ↑ in tacrolimus concentrations |
Concomitant administration of tacrolimus and clarithromycin may result in increased plasma levels of tacrolimus and increased risk of toxicity.
Theophylline
| P | Potential ↑ in theophylline concentrations |
Clarithromycin use in patients who are receiving theophylline may be associated with an increase of serum theophylline concentrations.
Monitoring of serum theophylline concentrations should be considered for patients receiving high doses of theophylline or with baseline concentrations in the upper therapeutic range.
Concomitant Drug
Name
| Ref. | Effect |
Clinical Comments
Tolterodine
| P | ↑ serum tolterodine concentrations |
The primary route of metabolism for tolterodine is via the 2D6 isoform of cytochrome P450 (CYP2D6). However, in a subset of the population devoid of CYP2D6, the identified pathway of metabolism is via CYP3A. In this population subset, inhibition of CYP3A results in significantly higher serum concentrations of tolterodine. A reduction of tolterodine dosage may be necessary in the presence of CYP3A inhibitors, such as clarithromycin in the CYP2D6 poor metabolizer population.
Triazolobenzo-diazepines
(e.g., triazolam, alprazolam)
Other related benzodiazepines (e.g., midazolam)
CT, C, P | ↑ midazolam AUC |
When midazolam was co-administered with clarithromycin tablets (500 mg twice daily), midazolam AUC was increased 2.7-fold after intravenous administration of midazolam and 7-fold after oral administration. Concomitant administration of oral midazolam and clarithromycin is contraindicated. See CONTRAINDICATIONS. If intravenous midazolam is co-administered with clarithromycin, the patient must be closely monitored to allow dose adjustment of midazolam.
The same precautions should also apply to other benzodiazepines that are metabolized by CYP3A, including triazolam and alprazolam. For benzodiazepines which are not dependent on CYP3A for their elimination (temazepam, nitrazepam, lorazepam), a clinically important interaction with clarithromycin is unlikely.
There have been post-marketing reports of drug interactions and central nervous system (CNS) effects (e.g., somnolence and confusion) with the concomitant use of clarithromycin and triazolam. Monitoring the patient for increased CNS pharmacological effects is suggested.
Zidovudine
| C | Potential ↓ in zidovudine concentrations |
Simultaneous oral administration of BIAXIN BID® tablets and zidovudine to HIV-infected adult patients may result in decreased steady-state zidovudine
concentrations. Clarithromycin appears to interfere with the absorption of simultaneously administered oral zidovudine, and therefore this interaction can be largely avoided by staggering the doses of clarithromycin and zidovudine.
Concomitant Drug
Name
| Ref. | Effect |
Clinical Comments
Others / Drugs
metabolized by CYP3A
(e.g., alfentanil, bromocriptine,
cilostazol,
methylprednisolone, vinblastine)
| C, P | Potential change in serum concentration |
Interactions with erythromycin and/or clarithromycin have been reported with a number of other drugs metabolized by CYP3A, such as alfentanil, bromocriptine, cilostazol, methylprednisolone, or vinblastine.
Serum concentrations of drugs metabolized by CYP3A should be monitored closely in patients concurrently receiving erythromycin or clarithromycin.
Other drugs
metabolized by cytochrome P450 isoforms other than CYP3A
(e.g., hexobarbital, phenytoin, and valproate)
| C, P | Potential change in serum concentration |
Interactions with erythromycin and/or clarithromycin have been reported with drugs metabolized by other cytochrome P450 isoforms (i.e., not CYP3A), such as hexobarbital, phenytoin, and valproate.
Serum concentrations of these drugs should be monitored closely in patients concurrently receiving erythromycin or clarithromycin.
Other drug inducers of the cytochrome P450 system
(e.g, efavirenz,
nevirapine, rifampin, rifabutin, rifampicin, phenobarbital,
rifapentine)
| CT, P | ↓ levels of clarithromycin |
Strong inducers of the cytochrome P450 metabolism system such as efavirenz, nevirapine, rifampin, rifabutin, rifampicin, phenobarbital and rifapentine* may accelerate the metabolism of clarithromycin and thus lower the plasma levels of clarithromycin, while increasing those of 14-OH-clarithromycin, a metabolite that is also microbiologically active.
Since the microbiological activities of clarithromycin and 14-OH-clarithromycin are different for different bacteria, the intended therapeutic effect could be impaired during concomitant administration of clarithromycin and enzyme inducers.
Legend: C = Case Study; CT = Clinical Trial; P = Potential
Interactions with other drugs have not been established.
* not marketed in Canada.
AMOXICILLIN (amoxicillin trihydrate) Capsules
Methotrexate: Penicillins compete with renal tubular secretion of methotrexate, resulting in decreased clearance of methotrexate. Concomitant use may increase methotrexate serum concentrations, with increased risk of toxicity.
Probenecid: Probenecid inhibits the renal tubular excretion of amoxicillin. Concurrent use of amoxicillin and probenecid may result in increased and prolonged blood levels of amoxicillin.
Warfarin: Abnormal prolongation of prothrombin time (increased international normalized ratio [INR]) has been reported in patients receiving amoxicillin and warfarin. Appropriate monitoring
should be undertaken when warfarin is prescribed concurrently. Adjustments in the dose of oral anticoagulants may be necessary to maintain the desired level of anticoagulation.
Oral contraceptives: Amoxicillin may affect the gut flora, leading to lower estrogen reabsorption and reduced efficacy of combined oral estrogen/progesterone contraceptives.
Tetracyclines: Bacteriostatic action of tetracyclines may inhibit bactericidal activity of penicillins.
Drug-Food Interactions
PREVACID® (lansoprazole delayed-release capsules)
Food reduces the peak concentration and the extent of absorption of lansoprazole by about 50% to 70%. Therefore, it is recommended that PREVACID® be administered in the morning prior to breakfast.
BIAXIN BID® (clarithromycin tablets, USP, film-coated)
BIAXIN BID® (clarithromycin tablets, USP, film-coated) may be given with or without meals.
Drug-Herb Interactions
BIAXIN BID® (clarithromycin tablets, USP, film-coated)
St. John’s Wort (Hypericum perforatum) is an inducer of CYP3A and may induce the metabolism of clarithromycin. This may result in sub-therapeutic levels of clarithromycin leading to reduced efficacy.
Drug-Laboratory Interactions
PREVACID® (lansoprazole delayed-release capsules)
During treatment with antisecretory drugs, chromogranin A (CgA) increases due to decreased gastric acidity. Increased Chromogranin A (CgA) level may interfere with investigations for neuroendocrine tumours. To avoid this interference, Hp-PAC® treatment should be stopped 14 days before CgA measurements (see ACTION AND CLINICAL PHARMACOLOGY, Pharmacodynamics, Pharmacodynamic Properties).
Drug-Lifestyle Interactions
BIAXIN BID® (clarithromycin tablets, USP, film-coated)
Effects on Ability to Drive and Use Machines
There are no data on the effect of clarithromycin on the ability to drive or use machines. The potential for dizziness, vertigo, confusion and disorientation, which may occur with the medication, should be taken into account before patients drive or use machines.
DOSAGE AND ADMINISTRATION
Dosing Considerations
Hp-PAC® Triple Therapy: PREVACID®/clarithromycin/amoxicillin
For the eradication of H. pylori, amoxicillin and clarithromycin should not be administered to patients with renal impairment since the appropriate dosage in this patient population has not yet been established.
PREVACID® (lansoprazole delayed-release capsules)
It is recommended that the initial dosing regimen need not be altered for patients with mild or moderate liver disease, but for patients with moderate impairment, doses higher than 30 mg / day should not be administered unless there are compelling clinical indications (see WARNINGS AND PRECAUTIONS, Hepatic/Biliary/Pancreatic).
Recommended Dose and Dosage Adjustment
Hp-PAC® Triple Therapy: PREVACID®/clarithromycin/amoxicillin
The recommended adult oral dose is 30 mg lansoprazole 500 mg clarithromycin, and 1000 mg amoxicillin, all given twice daily for 7, 10 or 14 days (see INDICATIONS AND CLINICAL USE). Daily doses should be taken before meals.
Patients should use the lowest dose and shortest duration of PPI therapy appropriate to the condition being treated.
Patients with Hepatic Impairment
The daily dose of lansoprazole should not exceed 30 mg (see WARNINGS AND PRECAUTIONS).
Clarithromycin may be administered without dosage adjustment in the presence of hepatic impairment if there is normal renal function. See CONTRAINDICATIONS and WARNINGS AND PRECAUTIONS.
Patients with Renal Impairment
PREVACID® (lansoprazole delayed-release capsules)
No dosage modification of lansoprazole is necessary (see WARNINGS AND PRECAUTIONS).
BIAXIN BID® (clarithromycin tablets, USP, film-coated)
Refer to WARNINGS AND PRECAUTIONS, Renal.
Elderly Patients
The daily dose of lansoprazole should not exceed 30 mg (see WARNINGS AND PRECAUTIONS).
Concomitant Antacid Use
Simultaneous administration of lansoprazole with aluminum and magnesium hydroxide or magaldrate results in lower peak plasma levels, but does not significantly reduce bioavailability. Antacids may be used concomitantly if required. If sucralfate is to be given concomitantly, lansoprazole should be administered at least 30 minutes prior to sucralfate (see ACTION AND CLINICAL PHARMACOLOGY, Pharmacokinetics, Absorption, Absorption with Antacids). In clinical trials, antacids were administered concomitantly with PREVACID® capsules; this did not interfere with its effect.
Missed Dose
Patients should be instructed that if a dose of this medication has been missed, it should be taken as soon as possible. However, if the next scheduled dose is due, the patient should not take the missed dose, and should be instructed to take the next dose on time. Patients should be instructed not to take 2 doses at one time to make up for a missed dose.
Administration
PREVACID® delayed-release capsules SHOULD NOT BE CRUSHED, CHEWED, BROKEN OR CUT.
OVERDOSAGE
For management of a suspected drug overdose, contact your regional Poison Control Centre.
Hp-PAC® Triple Therapy: PREVACID®/clarithromycin/amoxicillin
In case of an overdose, patients should contact a physician, poison control center, or emergency room. There is neither a pharmacologic basis nor any data suggesting an increase in the toxicity of the Hp-PAC® combination compared to its individual components.
PREVACID® (lansoprazole delayed-release capsules)
As in all cases where overdosing is suspected, treatment should be supportive and symptomatic. Any unabsorbed material should be removed from the gastrointestinal tract, and the patient should be carefully monitored. Lansoprazole is not removed from the circulation by hemodialysis. In one reported case of overdose, the patient consumed 600 mg of lansoprazole with no adverse reaction.
Oral doses up to 5000 mg/kg in rats (approximately 1300 times the recommended human dose based on body surface area) and mice (about 675.7 times the recommended human dose based on body surface area) did not produce deaths or any clinical signs.
BIAXIN BID® (clarithromycin tablets, USP, film-coated)
Reports indicate that the ingestion of large amounts of clarithromycin can be expected to produce gastrointestinal symptoms. Adverse reactions accompanying overdosage should be treated by the prompt elimination of unabsorbed drug and supportive measures. Clarithromycin is protein bound (70%). No data are available on the elimination of clarithromycin by hemodialysis or peritoneal dialysis.
AMOXICILLIN (amoxicillin trihydrate) Capsules
Treatment of overdosage would likely be needed only in patients with severely impaired renal function, since patients with normal kidneys excrete penicillins at a fast rate. Hemodialysis would therefore represent the main form of treatment.
Activated charcoal may be administered to aid in the removal of unabsorbed drug.General supportive measures are recommended.
ACTION AND CLINICAL PHARMACOLOGY
Mechanism of Action
PREVACID® (lansoprazole delayed-release capsules)
PREVACID® (lansoprazole delayed-release capsules inhibits the gastric H+, K+-ATPase (the proton pump) which catalyzes the exchange of H+ and K+. It is effective in the inhibition of both basal acid secretion and stimulated acid secretion.
BIAXIN BID® (clarithromycin tablets, USP, film-coated)
Clarithromycin exerts its antibacterial action by binding to the 50S ribosomal subunit of susceptible bacteria and suppressing protein synthesis.
Pharmacodynamics
Eradication of Helicobacter pylori
Helicobacter pylori is considered to be a major factor in the etiology of duodenal ulcer disease. The presence of H. pylori may damage the mucosal integrity due to the production of enzymes (catalase, lipases, phospholipases, proteases, and urease), adhesins and toxins; the inflammatory response generated in this manner contributes to mucosal damage.
The concomitant administration of an antimicrobial(s) such as clarithormycin and amoxicillin, and an antisecretory agent such as lansoprazole, improves the eradication of H. pylori as compared to individual drug administration. The higher pH resulting from antisecretory treatment, optimizes the environment for the pharmacologic action of the antimicrobial agent(s) against H. pylori.
PREVACID® (lansoprazole delayed-release capsules)
In healthy subjects, single and multiple doses of PREVACID® capsules (15 mg to 60 mg) have been shown to decrease significantly basal gastric acid output and to increase significantly mean gastric pH and percent of time at pH > 3 and 4. These doses have also been shown to reduce significantly meal-stimulated gastric acid output and gastric secretion volume. Single or multiple doses of lansoprazole delayed-release capsules (10 mg to 60 mg) reduced pentagastrin-stimulated acid output. In addition, lansoprazole delayed-release capsules have been demonstrated to reduce significantly basal and pentagastrin-stimulated gastric acid secretion among Duodenal Ulcer and hypersecretory patients, and basal gastric acid secretion among patients with Gastric Ulcer disease.
A dose-response effect was analyzed by considering the results from clinical pharmacology studies that evaluated more than one dose of lansoprazole delayed-release capsules. The results indicated that, in general, as the dose was increased from 7.5 mg to 30 mg, there was a decrease in mean gastric acid secretion and an increase in the average time spent at higher pH values (pH > 4).
The results of pharmacodynamic studies with lansoprazole delayed-release capsules in normal subjects suggest that doses of 7.5 to 10 mg are substantially less effective in inhibiting gastric acid secretion than doses of 15 mg or greater. In view of these results, the doses of lansoprazole delayed-release capsules evaluated in the principal clinical trials ranged from 15 mg to 60 mg daily.
Pharmacodynamic Properties
During treatment with antisecretory medicinal products, serum gastrin increases in response to the decreased acid secretion. Also CgA increases due to decreased gastric acidity. The increased CgA level may interfere with investigations for neuroendocrine tumours.
Available published evidence suggests that proton pump inhibitors should be discontinued 14 days prior to CgA measurements. This is to allow CgA levels that might be spuriously elevated following PPI treatment to return to reference range (see WARNINGS AND PRECAUTIONS, Interference with Laboratory Tests).
Pharmacokinetics
Hp-PAC® Triple Therapy: PREVACID®/clarithromycin/amoxicillin
The pharmacokinetics of the drugs when all three components of the Hp-PAC® (PREVACID® capsules, clarithromycin tablets and amoxicillin capsules) were co-administered, has not been studied. Studies have shown no clinically significant interactions between PREVACID® and amoxicillin or PREVACID® and clarithromycin when co-administered. There is no information about the gastric mucosal concentrations of PREVACID®, amoxicillin and clarithromycin after administration of these agents concomitantly. The systemic pharmacokinetic information presented below is based on studies in which each product was administered alone.
PREVACID® (lansoprazole delayed-release capsules)
PREVACID® capsules contain an enteric-coated granule formulation of lansoprazole to ensure that absorption of lansoprazole begins only after the granules leave the stomach (lansoprazole is acid-labile). Peak plasma concentrations of lansoprazole (Cmax) and the area under the plasma concentration curve (AUC) of lansoprazole are approximately proportional in doses from 15 mg to 60 mg after single-oral administration. Lansoprazole pharmacokinetics are unaltered by multiple dosing and the drug does not accumulate.
Lansoprazole is highly bioavailable when administered orally. In a definitive absolute bioavailability study, the absolute bioavailability was shown to be 86% for a 15 mg capsule and 80% for a 30 mg capsule. First pass effect is apparently minimal.
Table 8 summarizes the pharmacokinetic parameters (Tmax,T½, AUC and Cmax) of PREVACID® capsules in healthy subjects. For a summary of pharmacokinetic, metabolism and excretion data in animals, see DETAILED PHARMACOLOGY, Animal.
Table 8. Pharmacokinetic Parameters of Lansoprazole Delayed-Release Capsules Pooled Across
Phase I Studies
Parameter
| Tmax (h) | T½ (h) | AUC* (ng•h/mL) |
Cmax* (ng/mL)
Mean
| 1.68 | 1.53 | 2133 |
824
Median
| 1.50 | 1.24 | 1644 |
770
SD
| 0.80 | 1.01 | 1797 |
419
% CV
| 47.71 | 65.92 | 84.28 |
50.81
Min
| 0.50 | 0.39 | 213 |
27
Max
| 6.00 | 8.50 | 14203 |
2440
N†
| 345 | 285 | 513 |
515
* Normalized to a 30 mg dose
† Number of dosages associated with a parameter
BIAXIN BID® (clarithromycin tablets, USP, film-coated)
A summary of clarithromycin pharmacokinetic parameters following the administration of clarithromycin film-coated tablets is provided in Table 9. For details see DETAILED PHARMACOLOGY in PART II of the Product Monograph.
Table 9. Clarithromycin Pharmacokinetic Parameters Following the Administration of
Clarithromycin Film-Coated Tablets
Single Dose*
Cmax (mg/L) | tmax (hr) | t½ (hr) |
AUC0-t
(mg·hr/L)
250 mg Mean
| 1 | 1.5 | 2.7 |
5.47
500 mg Mean
| 1.77 | 2.2 | -- |
11.66
Multiple Doses**
250 mg b.i.d. Mean
| 1 | -- | 3 to 4 |
6.34
500 mg b.i.d. Mean
| 3.38 | 2.1 | 5 to 7 |
44.19
* Single doses (from Tables 60 and 61)
** Multiple doses (from Tables 54 and 61)
Legend: b.i.d. = twice daily
Absorption
PREVACID® (lansoprazole delayed-release capsules)
The absorption of lansoprazole is rapid, with mean peak plasma levels of lansoprazole occurring at approximately 1.7 hours. Peak plasma concentrations of lansoprazole (Cmax) and the area
under the plasma concentration curve (AUC) are approximately proportional to dose throughout the range that has been studied (up to 60 mg).
Absorption with Food
Food reduces the peak concentration and the extent of absorption by about 50% to 70%. Moreover, the results of a pharmacokinetic study that compared the bioavailability of lansoprazole following a.m. dosing (fasting) versus p.m. dosing (3 hours after a meal) indicated that both Cmax and AUC values were increased by approximately 2-fold or more with a.m. dosing. Therefore, it is recommended that PREVACID® capsules be administered in the morning prior to breakfast.
Absorption with Antacids
Simultaneous administration of lansoprazole delayed-release capsules with aluminum and magnesium hydroxide or magaldrate resulted in lower peak serum levels, but did not significantly reduce the bioavailability of lansoprazole.
In a single-dose crossover study when 30 mg of lansoprazole was administered concomitantly with 1 gram of sucralfate in healthy volunteers, absorption of lansoprazole was delayed and its bioavailability was reduced. The value of lansoprazole AUC was reduced by 17% and that for Cmax was reduced by 21%.
In a similar study when 30 mg of lansoprazole was administered concomitantly with 2 grams of sucralfate, lansoprazole AUC and Cmax were reduced by 32% and 55%, respectively. When lansoprazole dosing occurred 30 minutes prior to sucralfate administration, Cmax was reduced by only 28% and there was no statistically significant difference in lansoprazole AUC. Therefore, lansoprazole may be given concomitantly with antacids but should be administered at least 30 minutes prior to sucralfate.
BIAXIN BID® (clarithromycin tablets, USP, film-coated)
The absolute bioavailability of 250 mg and 500 mg clarithromycin tablets is approximately 50%. Food slightly delays the onset of clarithromycin absorption but does not affect the extent of bioavailability. Therefore, BIAXIN BID® tablets may be given without regard to meals.
In fasting healthy human subjects, peak serum concentrations are attained within 2 hours after oral dosing. Steady-state peak serum clarithromycin concentrations, which are attained within 2 to 3 days, are approximately 1 mg/L with a 250 mg dose twice daily and 2 to 3 mg/L with a 500 mg dose twice daily. The elimination half-life of clarithromycin is about 3 to 4 hours with 250 mg twice daily dosing but increases to about 5 to 7 hours with 500 mg administered twice daily.
Clarithromycin displays non-linear pharmacokinetics at clinically relevant doses, producing greater than proportional increases in AUC with increasing dose. The degree of non-linearity is reduced on chronic clarithromycin administration (i.e., at steady state). The non-linearity of the
pharmacokinetics of the principle metabolite, 14-OH clarithromycin, is slight at the recommended doses of 250 mg and 500 mg administered twice daily. With 250 mg twice daily, 14-OH clarithromycin attains a peak steady state concentration of about 0.6 mg/L and has an elimination half-life of 5 to 6 hours. With a 500 mg twice daily dose, the peak steady-state of 14-OH concentrations of clarithromycin are slightly higher (up to 1 mg/L) and its elimination half-life is about 7 hours. With either dose, the steady-state concentration of this metabolite is generally attained within 2 to 3 days.
Adult Patients with HIV
Steady-state concentrations of clarithromycin and 14-OH clarithromycin observed following administration of 500 mg doses of clarithromycin twice a day to adult patients with HIV infection were similar to those observed in healthy volunteers. However, at the higher clarithromycin doses which may be required to treat mycobacterial infections, clarithromycin concentrations can be much higher than those observed at 500 mg clarithromycin doses. In adult HIV-infected patients taking 2000 mg/day in two divided doses, steady-state clarithromycin Cmax values ranged from 5 to10 mg/L. Cmax values as high as 27 mg/L have been observed in HIV-infected adult patients taking 4000 mg/day in two divided doses of clarithromycin tablets.
Elimination half-lives appeared to be lengthened at these higher doses as well. The higher clarithromycin concentrations and longer elimination half-lives observed at these doses are consistent with the known non-linearity in clarithromycin pharmacokinetics.
Clarithromycin and omeprazole
Clarithromycin 500 mg three times daily and omeprazole 40 mg once daily were studied in fasting healthy adult subjects. When clarithromycin was given alone as 500 mg every 8 hours, the mean steady state Cmax value was approximately 3.8 mcg/mL and the mean Cmin value was approximately 1.8 mcg/mL. The mean AUC0-8 for clarithromycin was 22.9 mcg•hr/mL. The Tmax and half life were 2.1 hrs and 5.3 hrs, respectively, when clarithromycin was dosed at 500 mg t.i.d. When clarithromycin was administered with omeprazole, increases in omeprazole half-life and AUC0-24 were observed. For all subjects combined, the mean omeprazole AUC0-24 was 89% greater and the harmonic mean for omeprazole t½ was 34% greater when omeprazole was administered with clarithromycin than when omeprazole was administered alone. When clarithromycin was administered with omeprazole, the steady state Cmax, Cmin, and AUC0-8 of clarithromycin were increased by 10%, 27%, and 15%, respectively over values achieved when clarithromycin was administered with placebo.
AMOXICILLIN (amoxicillin trihydrate) Capsules
Amoxicillin is stable in the presence of gastric acid and is well absorbed from the gastrointestinal tract and may be given with no regard to food. The half-life of amoxicillin is 61.3 minutes.
Orally administered doses of 500 mg amoxicillin capsules result in average peak blood levels 1 to 2 hours after administration in the range of 5.5 to 7.5 mcg/mL.
Detectable serum levels are observed up to 8 hours after an orally administered does of amoxicillin.
Distribution
PREVACID® (lansoprazole delayed-release capsules)
The apparent volume of distribution of lansoprazole is approximately 15.7 (± 1.9) L, distributing mainly in extracellular fluid. Lansoprazole is 97% bound to plasma proteins. The mean total body clearance (CL) of lansoprazole was calculated at 31 ± 8 L/h, and the volume of distribution (Vss) was calculated to be 29 (± 4) L.
BIAXIN BID® (clarithromycin tablets, USP, film-coated)
Clarithromycin distributes readily into body tissues and fluids, and provides tissue concentrations that are higher than serum concentrations. Examples from tissue and serum concentrations are presented in Table 10.
Table 10. Representative Clarithromycin Tissue and Serum Concentrations Following the
Administration of 250 mg b.i.d of Clarithromycin Film-Coated Tablets
Tissue Type
Concentrations
Tissue (mcg/g) Serum (mg/L)
Tonsil
Lung
Leukocytes*
1.6
8.8
9.2
0.8
1.7
1.0 * in vitro data.
Legend: b.i.d. = twice daily
AMOXICILLIN (amoxicillin trihydrate) Capsules
Amoxicillin diffuses readily into most body tissues and fluids, with the exception of brain and spinal fluid, except when the meninges are inflamed. Amoxicillin is not highly protein-bound. In serum, amoxicillin is approximately 20% protein-bound as compared to 60% for penicillin G.
Metabolism
PREVACID® (lansoprazole delayed-release capsules)
Lansoprazole is extensively metabolized in the liver. Two metabolites have been identified in measurable quantities in plasma; the hydroxylated sulfinyl and the sulfone derivatives of lansoprazole. These metabolites have very little or no antisecretory activity. Lansoprazole is thought to be transformed into 2 active species that inhibit acid secretion by blocking the proton pump (H+,K+)-ATPase enzyme system at the secretory surface of the gastric parietal cell. The 2 active species are not present in the systemic circulation. The plasma elimination half-life of lansoprazole is less than 2 hours while the acid inhibitory effect lasts over 24 hours. Therefore,
the plasma elimination half-life of lansoprazole does not reflect the duration of suppression of gastric acid secretion.
BIAXIN BID® (clarithromycin tablets, USP, film-coated)
Clarithromycin is principally excreted by the liver and kidney. The major metabolite found in urine is 14-OH-clarithromycin.
Excretion
PREVACID® (lansoprazole delayed-release capsules)
Following single dose oral administration of lansoprazole, virtually no unchanged lansoprazole was excreted in the urine. After a 30 mg single oral dose of 14C-lansoprazole, approximately one-third of the dose was excreted in the urine and approximately two-thirds were recovered in the feces. This implies a significant biliary excretion of the metabolites of lansoprazole.
BIAXIN BID® (clarithromycin tablets, USP, film-coated)
At 250 mg twice daily, approximately 20% of an orally administered dose of clarithromycin film-coated tablet is excreted in the urine as the unchanged parent drug. The urinary excretion of unchanged clarithromycin is somewhat greater (approximately 30%) with 500 mg twice daily dosing. The renal clearance of clarithromycin is, however, relatively independent of the dose size and approximates the normal glomerular filtration rate. The major metabolite found in urine is 14-OH-clarithromycin which accounts for an additional 10 to 15% of the dose with twice daily dosing at either 250 mg or 500 mg. Most of the remainder of the dose is eliminated in the feces, primarily via the bile. About 5 to 10% of the parent drug is recovered from the feces. Fecal metabolites are largely products of N-demethylation, 14-hydroxylation or both.
AMOXICILLIN (amoxicillin trihydrate) Capsules
Most of the amoxicillin is excreted unchanged in urine; its excretion can be delayed by concurrent administration of probenecid.
Approximately 60% of an orally administered dose of amoxicillin is excreted in the urine within 6 to 8 hours.
Special Populations and Conditions
Pediatrics
Hp-PAC® Triple Therapy: PREVACID®/clarithromycin/amoxicillin
The safety and effectiveness of Hp-PAC® in pediatric patients infected with H. pylori have not been established.
Geriatrics
PREVACID® (lansoprazole delayed-release capsules)
The results from the studies that evaluated the pharmacokinetics of lansoprazole following oral administration in an older population revealed that in comparison with younger subjects, older subjects exhibited significantly larger AUCs and longer t½s. Lansoprazole did not accumulate in the older subjects upon multiple dosing since the longest mean t½ in the studies was 2.9 hours, and lansoprazole is dosed once daily. Cmax in the elderly was comparable to that found in adult subjects.
BIAXIN BID® (clarithromycin tablets, USP, film-coated)
In a steady-state study in which healthy elderly subjects (age 65 to 81 years old) were given 500 mg of clarithromycin every 12 hours, the maximum concentrations of clarithromycin and 14-OH clarithromycin were increased. The AUC was also increased. These changes in pharmacokinetics parallel known age-related decreases in renal function. In clinical trials, elderly patients did not have an increased incidence of adverse events when compared to younger patients (see WARNINGS AND PRECAUTIONS, Renal).
Gender
In a study comparing 12 male and 6 female subjects, no gender differences were found in pharmacokinetics or intragastric pH results (see PRECAUTIONS, Use in Women).
Race
The pooled pharmacokinetic parameters of oral administered lansoprazole from 12 U.S. Phase I studies (N=513) were compared to the mean pharmacokinetic parameters from 2 Asian studies (N=20). The mean AUCs of lansoprazole in Asian subjects are approximately twice that seen in pooled U.S. data, however, the inter-individual variability is high. The Cmax values are comparable.
Hepatic Insufficiency
PREVACID® (lansoprazole delayed-release capsules)
As would be expected with a drug that is primarily metabolized by the liver, in patients with mild (Child-Pugh Class A) or moderate (Child-Pugh Class B) chronic hepatic disease, the plasma half-life of the drug after oral administration increased to 5.2 hours compared to the 1.5 hours half-life in healthy subjects. An increase in AUC of 3.4 fold was observed in patients with hepatic impairment versus healthy subjects (7096 versus 2645 ng•h/mL) which was due to slower elimination of lansoprazole; however, Cmax was not significantly affected. Dose reduction in patients with severe hepatic disease should be considered.
BIAXIN BID® (clarithromycin tablets, USP, film-coated)
The steady-state concentrations of clarithromycin in subjects with impaired hepatic function did not differ from those in normal subjects; however, the 14-OH clarithromycin concentrations were lower in the hepatically impaired subjects. The decreased formation of 14-OH clarithromycin was at least partially offset by an increase in renal clearance of clarithromycin in subjects with impaired hepatic function when compared to healthy subjects (see WARNINGS AND PRECAUTIONS and DOSAGE AND ADMINISTRATION).
Renal Insufficiency
PREVACID® (lansoprazole delayed-release capsules)
In patients with mild (Clcr 40 to 80 mL/min), moderate (Clcr 20 to 40 mL/min) and severe (Clcr < 20 mL/min) chronic renal impairment, the disposition of lansoprazole after oral administration was very similar to that of healthy volunteers.
The impact of dialysis on lansoprazole was evaluated from a pharmacokinetic standpoint, and there were no significant differences in AUC, Cmax or t ½ between dialysis day and dialysis-free day. Dialysate contained no measurable lansoprazole or metabolite. Lansoprazole is not significantly dialysed.
BIAXIN BID® (clarithromycin tablets, USP, film-coated)
The pharmacokinetics of clarithromycin was also altered in subjects with impaired renal function. The elimination of clarithromycin was impaired in patients with impaired renal function (see WARNINGS AND PRECAUTIONS, Renal and DOSAGE AND ADMINISTRATION).
AMOXICILLIN (amoxicillin trihydrate) Capsules
In the presence of renal impairment the serum half life increases (between 7 and 10 hours), necessitating a reduction in the dosage administred. See WARNINGS AND PRECAUTIONS, Renal.
STORAGE AND STABILITY
Store the Hp-PAC® blister cards between 15 and 25°C. Protect from light and moisture.
DOSAGE FORMS, COMPOSITION AND PACKAGING
Composition
Hp-PAC® - H. pylori Individual Daily Administration Blister Pack
Hp-PAC® daily administration blister packs are available in boxes containing seven (7) days of therapy. Each triple therapy Hp-PAC® (lansoprazole/clarithromycin/amoxicillin) daily administration blister pack contains:
PREVACID® (lansoprazole delayed-release capsules):
two opaque, hard gelatin, pink and black lansoprazole 30 mg capsules, with the TAP logo and “PREVACID 30" imprinted on the capsules.
Medicinal Ingredient: Each delayed-release capsule contains 30 mg of lansoprazole in the form of enteric-coated granules for oral administration.
Non-Medicinal Ingredients: Each PREVACID® delayed-release capsule also contains the following non-medicinal ingredients: colloidal silicon dioxide, D&C Red No. 28, FD&C Blue No. 1, FD&C Red No. 40, gelatin, hydroxypropyl cellulose, low substituted hydroxypropyl cellulose, magnesium carbonate, methacrylic acid copolymer, starch, talc, sugar spheres, sucrose, polyethylene glycol, polysorbate 80, and titanium dioxide.
BIAXIN BID® (clarithromycin tablets, USP, film-coated):
two pale yellow, oval, film-coated clarithromycin 500 mg tablets, with the logo ‘M’ printed on one side.
Medicinal Ingredient: Each oval, printed with logo ‘M’ on one side, pale yellow film-coated BIAXIN BID® tablet contains 500 mg of clarithromycin for oral administration.
Non-Medicinal Ingredients: Each BIAXIN BID® 500 mg tablet also contains the following non-medicinal ingredients: cellulosic polymers, croscarmellose sodium, D&C Yellow No.10, magnesium stearate, povidone, propylene glycol, silicon dioxide, sorbic acid, sorbitan monooleate, stearic acid, talc, titanium dioxide and vanillin. BIAXIN BID® does not contain tartrazine.
AMOXICILLIN (amoxicillin trihydrate) Capsules:
four opaque, scarlet and gold amoxicillin capsules, with the logo ‘M’ and “500"
imprinted on the capsules.
Medicinal Ingredient: Each amoxicillin capsule contains amoxicillin trihydrate equivalent to 500 mg of amoxicillin.
Non-Medicinal Ingredients: Each Amoxicillin 500 mg capsule also contains the following non-medicinal ingredients: colloidal silicon dioxide, ECG size #0, dry-flo starch, magnesium stearate, sodium lauryl sulfate, and talc. Gluten- and tartrazine-free. 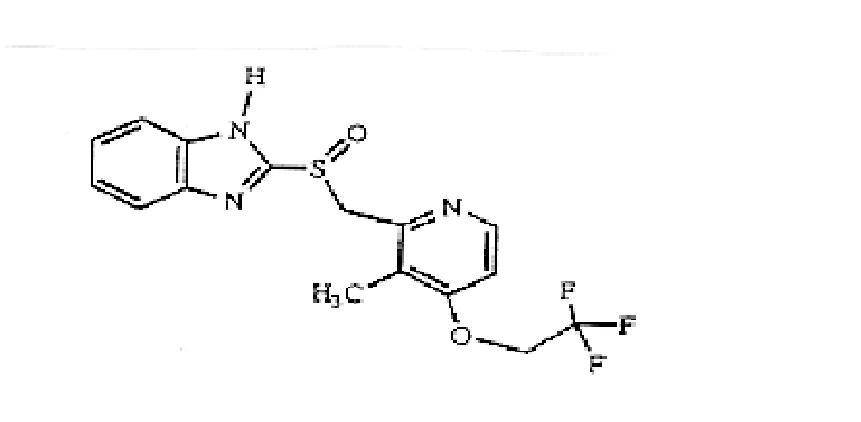
PART II: SCIENTIFIC INFORMATION
PHARMACEUTICAL INFORMATION
Drug Substance
PREVACID® (lansoprazole delayed-release capsules)
Proper name: Lansoprazole
Chemical name: 2-[[[3-methyl-4-(2,2,2-trifluoroethoxy)-2-pyridyl]methyl]sulfinyl]-benzimidazole
Molecular formula
and molecular
mass:
C16H14F3N3O2S
369.37
Structural formula:
Physicochemical
properties:
Lansoprazole is a white to brownish-white odourless, crystalline powder which melts with decomposition at approximately 166°C. Lansoprazole is freely soluble in dimethylformamide; slightly soluble in methanol; sparingly soluble in ethanol; slightly soluble in ethyl acetate, dichloromethane and acetonitrile; very slightly soluble in ether; and practically insoluble in water and hexane.
The rate of degradation of the compound in aqueous solution increases with decreasing pH. It has an octanol/water partition coefficient of 240 at pH 7.
BIAXIN BID® (clarithromycin tablets, USP, film-coated)
Proper name: Clarithromycin
Chemical name: (3R*, 4S*, 5S*, 6R*, 7R*, 9R*, 11R*, 12R*, 13S*, 14R*)-4-[(2,6-dideoxy-3-C-methyl-3-0-methyl-alpha-L-ribo-hexopyranosyl)oxy]-14-ethyl-12,13-dihydroxy-7-methoxy-3,5,7,9,11,13-hexamethyl-6-[[3,4,6-trideoxy-3-(dimethylamino)-beta-D-xylo-
hexopyranosyl]oxy]oxacyclotetradecane-2-10-dione.
Molecular formula
and molecular
mass:
C38H69NO13 747.96
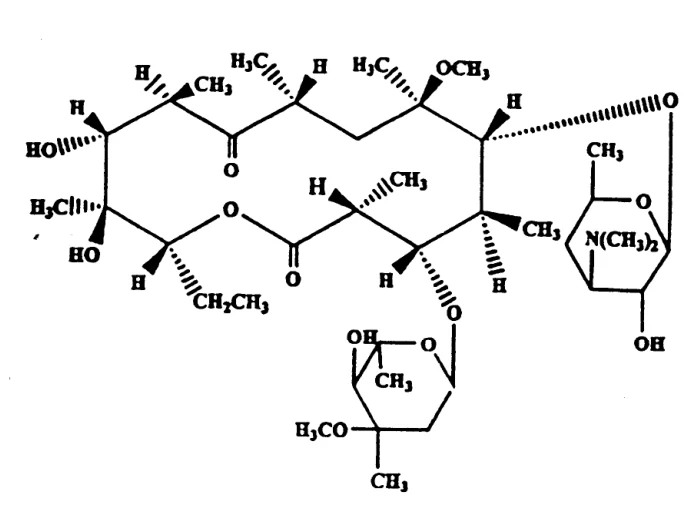
Structural formula:
Physicochemical
properties:
Clarithromycin is a white to off-white crystalline powder. It is slightly soluble in methanol, ethanol and acetonitrile, and practically insoluble in water. The pKa of clarithromycin is 8.48; the pH of a 0.2% (Methanol:Water, 5:95) slurry is 8.8.
The partition coefficient of clarithromycin is influenced by the pH of the water phase and polarity of the organic phase. For octanol (dipole moment = 0.25): water, the partition co-efficient varies from 5.63 to 46.0 for pH water increases from 2 to 8. The melting point of clarithromycin is approximately 225ΕC.
AMOXICILLIN (amoxicillin trihydrate) Capsules
Proper name: amoxicillin trihydrate
Chemical name: trihydrate of 6–[D–(–)–alpha–amino–4–hydroxyphenyl–acetamido]– penicillanic acid.
Molecular formula
and molecular
mass:
C16H19N3O5S·3H2O 419.5
Structural formula:

HO
N
H
O
H2N H
N
H H S
CH3 H
CH3 O
O
HO
3H2O
Physicochemical
properties:
Amoxicillin trihydrate is a white practically odourless crystalline powder, slightly soluble in water and in methanol; insoluble in benzenes, in chloroform and in ether.
CLINICAL TRIALS
Helicobacter pylori Eradication to Reduce the Risk of Duodenal Ulcer Recurrence
Randomized, double-blind clinical studies in patients with Helicobacter pylori (H. pylori) and duodenal ulcer disease (defined as an active ulcer or history of an ulcer within 1 year) evaluated the efficacy of lansoprazole delayed-release capsules in combination with amoxicillin capsules and clarithromycin tablets as triple 14-day therapy, or lansoprazole delayed-release capsules in combination with amoxicillin as dual 14-day therapy for the eradication of H. pylori. Based on the results of these studies, the safety and efficacy of 2 different eradication regimens were established:
Triple therapy: PREVACID® 30 mg twice daily/clarithromycin 500 mg twice daily/ amoxicillin 1000 mg twice daily
All treatments were for 14 days. H pylori eradication was defined as 2 negative tests (culture and histology) at 4 to 6 weeks following the end of treatment.
Triple therapy was shown to be more effective than all possible dual therapy combinations (Table 11). Eradication of H. pylori has been shown to reduce the risk of duodenal ulcer recurrence.
A randomized, double-blind clinical study performed in the U.S. in patients with H. pylori and duodenal ulcer disease (defined as an active ulcer or history of an ulcer within 1 year) compared the efficacy of PREVACID® capsules triple therapy for 10 and 14 days. This study established that the 10-day triple therapy was equivalent to the 14-day triple therapy in eradicating H. pylori (Table 11).
Table 11. H. pylori Eradication Rates - Triple Therapy (PREVACID®/clarithromycin/amoxicillin)
Percent of Patients Cured [95% Confidence Interval] (Number of Patients)
Study
| Duration | Triple Therapy Evaluable Analysis* |
Triple Therapy Intent-to-Treat Analysis†
#1
(M93-131)
| 14 days | 92‡ [80.0-97.7] (N=48) |
86‡
[73.3-93.5]
(N=55)
#2
(M95-392)
| 14 days | 86§ [75.7-93.6] (N=66) |
83§
[72.0-90.8]
(N=70)
#3
(M95-399) ¶
| 14 days | 85 [77.0-91.0] (N=113) |
82
[73.9-88.1]
(N=126)
| 10 days | 84 [76.0-89.8] (N=123) |
81
[73.9-87.6]
(N=135)
* Based on evaluable patients with confirmed duodenal ulcer (active or within 1 year) and H. pylori infection at baseline defined as at least 2 of 3 positive endoscopic tests from CLOtest® (Delta West Ltd., Bentley, Australia), histology and/or culture. Patients were included in the analysis if they completed the study. Additionally, if patients dropped out of the study due to an adverse event related to the study drug, they were included in the analysis as failures of therapy. † Patients were included in the analysis if they had documented H. pylori infection at baseline as defined above and had a confirmed duodenal ulcer (active or within 1 year). All dropouts were included as failures of therapy. ‡ (p < 0.05) versus PREVACID/amoxicillin and PREVACID/clarithromycin dual therapy.
§ (p < 0.05) versus clarithromycin/amoxicillin dual therapy.
¶ The 95% confidence interval for the difference in eradication rates, 10-day minus 14-days is (-10.5, 8.1) in the evaluable analysis and (-9.7, 9.1) in the intent-to-treat analysis.
A randomized, open-label, parallel-group, multicenter clinical study performed in the U.K. in patients with H. pylori and duodenal ulcer disease and/or gastritis, compared the efficacy and safety of four 7-day triple therapy treatment regimens. The primary efficacy measure was eradication of H. pylori as defined by a negative 13C-urea breath test at least 28 days (Visit 3) after completing study medication. This study established that 7-day triple therapy with PREVACID®/clarithromycin/amoxicillin was as clinically effective in eradication H. pylori as the 10- or 14-day treatment regimens (Table 12).
Table 12. Post-treatment Breath Test Results by Patient Population H. pylori Eradication Rates -
Triple Therapy Regimen (PREVACID®/clarithromycin/amoxicillin)
Population
Trial # 4 (GB 94/110)
PREVACID® 30 mg twice daily + clarithromycin 250 mg twice daily + amoxicillin 1000 mg twice daily
Evaluable (Per Protocol)*
Positive n (%) 11 (9.6)
Negative n (%) 103 (90.4)
95% CI (eradication rate) 83.0, 94.8
Intent-to-treat#
Positive n (%) 12 (10.3)
Negative n (%) 104 (89.7)
95% CI (eradication rate) 82.3, 94.3
Intent-to-treat (Worst case) †
Positive n (%) 17 (14.0)
Negative n (%) 104 (86.0)
95% CI (eradication rate) 78.2, 91.4
Intent-to-treat (Best case)†
Positive n (%) 12 (9.9)
Negative n (%) 109 (90.1)
95% CI (eradication rate) 83.0, 94.5
* Based on evaluable patients with confirmed duodenal ulcer and /or gastritis and H. pylori infection at baseline defined as at least 2 of 3 positive endoscopic tests from CLOtest®, histology and/or culture. Patients were included in the analysis if they completed the study. Additionally, if patients dropped out of the study due to an adverse event related to the study drug, they were included in the analysis as failures of therapy.
† “Worst case” assumed that missing Visit 3 breath test results were positive for H. pylori and “Best case” results assumed that missing Visit 3 results were negative for H. pylori.
# Patients were included in the analysis if they had documented H. pylori infection at baseline as defined above and had a confirmed duodenal ulcer.
A combination of PREVACID® plus clarithromycin and amoxicillin as triple therapy, was effective in eradicating H. pylori. Eradication of H. pylori has been shown to reduce the risk of duodenal ulcer recurrence.
There were no statistically significant differences in H. pylori eradication rates between the levels of any potentially influential factors, including baseline duodenal ulcer status, baseline duodenal ulcer size, gender, age, race, or tobacco use for the evaluable, intent-to-treat (all available data), and modified intent-to-treat (worst case) analyses. H. pylori eradication rates at the Week 6 Visit for patients who received lansoprazole 30 mg twice daily, clarithromycin 500 mg twice daily, and amoxicillin 1000 mg twice daily are presented by concomitant factors in Table 13 and Table 14 for the 14-day and 10-day treatment studies, respectively.
A statistically significant difference in ulcer prevalence rates was observed between the levels for age in the evaluable, intent-to-treat (all available data), and modified intent-to-treat (worst case) analyses, with younger patients demonstrating a lower ulcer prevalence rate compared with older patients. No statistically significant differences in ulcer prevalence rates were observed between the levels of other potentially influential factors including baseline duodenal ulcer status, baseline duodenal ulcer size, gender, race, or tobacco use for the evaluable, intent-to-treat (all available data), and modified intent-to-treat (worst case) analyses.
A statistically significant difference in H. pylori eradication rates was observed between the levels of baseline duodenal ulcer size in the evaluable and intent-to-treat (all available data) analyses, with patients who had smaller ulcers (3 to 5 mm) demonstrating a lower H. pylori eradication rate compared with patients who had larger ulcers. Statistically significant differences in H. pylori eradication rates were also observed between the levels of age in the intent-to-treat (all available data) and modified intent-to-treat (worst case) analyses, with patients over 65 years of age demonstrating a higher H. pylori eradication rate compared with patients less than or equal to 65 years of age. No statistically significant differences in H. pylori eradication rates were observed between the levels of other potentially influential factors including baseline duodenal ulcer status, gender, race, or tobacco use for the evaluable, intent-to-treat (all available data), and modified intent-to-treat (worst case) analyses.
Table 13. H. pylori Eradication Rates at the Week 6 Visit for Patients Who Received 14 days of
PREVACID® 30 mg Twice Daily, Clarithromycin 500 mg Twice Daily, and Amoxicillin 1000 mg Twice Daily by Concomitant Factors
Factor % (n/N)
Evaluable Intent-to-Treat
(All Available Data)
Modified Intent-to-Treat
(Worst Case)
Baseline Duodenal Ulcer Status
Active
| 88% (88/100) | 89% (91/102) |
83% (91/110)
Historical
| 93% (13/14) | 93% (14/15) |
93% (14/15)
Baseline Duodenal Ulcer Size
3 to 5 mm
| 85% (23/27) | 86% (24/28) |
83% (24/29)
> 5 to 10 mm
| 89% (55/62) | 92% (57/62) |
84% (57/68)
> 10 mm
| 91% (10/11) | 83% (10/12) |
77% (10/13)
Gender
Female
| 89% (31/35) | 89% (32/36) |
84% (32/38)
Male
| 89% (70/79) | 90% (73/81) |
84% (73/87)
Age
< 45
| 87% (46/53) | 88% (50/57) |
83% (50/60)
45 to 65
| 92% (43/47) | 92% (43/47) |
84% (43/51)
> 65
| 86% (12/14) | 92% (12/13) |
86% (12/14)
Race
| 82% (22/27) | 82% (23/28) |
79% (23/29)
Caucasian
| 92% (57/62) | 91% (59/65) |
83% (59/71)
Other
| 88% (22/25) | 96% (23/24) |
92% (23/25)
Tobacco Use
Nonuser*
| 89% (56/63) | 92% (58/63) |
87% (58/67)
User
| 88% (45/51) | 87% (47/54) |
81% (47/58)
No statistically significant differences were observed between the levels of any factor after stratification by study. * Includes ex-tobacco users
Table 14. H. pylori Eradication Rates at the Week 6 Visit for Patients Who Received 10 days of
PREVACID® 30 mg Twice Daily, Clarithromycin 500 mg Twice Daily, and Amoxicillin 1000 mg Twice Daily by Concomitant Factors
Factor % (n/N)
Evaluable Intent-to-Treat
(All Available Data)
Modified Intent-to-Treat
(Worst Case)
Baseline Duodenal Ulcer Status
Active
| 86% (91/106) | 88% (97/110) |
83% (97/117)
Historical
| 71% (12/17) | 72% (13/18) |
72% (13/18)
Baseline Duodenal Ulcer Size*
3 to 5 mm
| 77% (34/44) | 80% (36/45) |
75% (36/48)
> 5 to 10 mm
| 91% (43/47) | 94% (47/50) |
90% (47/52)
> 10 mm
| 93% (14/15) | 93% (14/15) |
82% (14/17)
Gender
Female
| 79% (38/48) | 82% (42/51) |
79% (42/53)
Male
| 87% (65/75) | 88% (68/77) |
83% (68/82)
Age
< 45
| 85% (33/39) | 85% (35/41) |
80% (35/44)
45 to 65
| 82% (56/68) | 86% (61/71) |
81% (61/75)
> 65
| 88% (14/16) | 88% (14/16) |
88% (14/16)
Race
| 84% (16/19) | 90% (18/20) |
78% (18/23)
Caucasian
| 82% (62/76) | 83% (66/80) |
80% (66/82)
Other
| 89% (25/28) | 93% (26/28) |
87% (26/30)
Tobacco Use
Nonuser†
| 83% (59/71) | 87% (65/75) |
81% (65/80)
User
| 85% (44/52) | 85% (45/53) |
82% (45/55)
No statistically significant differences were observed among the levels of any factor.
* Includes only patients with active duodenal ulcer at baseline
† Includes ex-tobacco users
A statistically significant difference in ulcer prevalence rates was observed between baseline duodenal ulcer status (active or historical) in the evaluable, intent-to-treat (all available data), and modified intent-to-treat (worst case) analyses, with patients who had a historical duodenal ulcer at baseline demonstrating a lower ulcer prevalence rate compared with patients who had an active duodenal ulcer at baseline. No statistically significant differences in ulcer prevalence rates were observed among the levels of other potentially influential factors including baseline duodenal ulcer size, gender, age, race, or tobacco use for the evaluable, intent-to-treat (all available data), and modified intent-to-treat (worst case) analyses.
DETAILED PHARMACOLOGY
Animal
Pharmacodynamics
PREVACID® (lansoprazole delayed-release capsules)
Studies of the preclinical pharmacology of lansoprazole have delineated its mechanism of action with in vitro investigations and have demonstrated in vivo efficacy. The orally administered compound appears to gain access to gastric parietal cells as the uncharged parent with conversion in the secretory canaliculus to charged metabolites that bind directly to a sulfhydryl group on the canalicular (H+,K+)-ATPase. In vivo comparisons with the histamine H2-receptor antagonist (H2-RA) famotidine have revealed that in preventing ulcer induction or in accelerating healing, famotidine shows greater potency but is not as universal in its effect as lansoprazole. Famotidine fails to suppress acid secretion induced by stress and deoxyglucose and also fails to prevent gastric lesions induced by ethanol. Further, famotidine is significantly less potent than lansoprazole in preventing esophagitis resulting from reflux and decreased mucosal resistance. Chronically, famotidine is significantly less potent than lansoprazole in healing gastric ulcers and duodenal ulcers.
These data suggest that lansoprazole has a potency profile comparable to that of another proton-pump inhibitor, omeprazole; while potency with respect to H2-RAs may not be as great, more comprehensive suppression of acid secretion is achieved with associated acceleration of lesion healing.
General pharmacology investigations have not revealed identifiable tendencies in animal models for lansoprazole to induce untoward side effects. No contraindicated effects could be detected in the gastrointestinal (GI) system. Smooth muscle contraction and GI transit are unaffected by lansoprazole at doses 200 times greater than those anticipated in humans. Beneficial effects of the compound have been observed on gastric hemodynamics in experimental shock. No notable neuropharmacologic results have been observed. No effects of lansoprazole have been observed on muscle relaxation, anticonvulsant activity, analgesia, or hypothermic responses. Both central and autonomic responses are also free of detectable effects of the compound.
Results on cardiovascular pharmacology are, similarly, without physiologic significance. No notable effects were observed on blood pressure, heart rate, or respiration at doses in excess of 600-fold greater than the anticipated dose in humans. Similarly, water and electrolyte balance are unperturbed by lansoprazole.
The combination of both in vitro and in vivo efficacy for this inhibitor of the gastric proton pump has been demonstrated to be comparable to another member of its class, omeprazole. Its efficacy profile has been found superior to a representative H2-RA, famotidine. Notable absence of
untoward side effects has been demonstrated over a wide range of animal species and suggests a highly specific site of action in the acid secretory compartment of the gastric parietal cell.
Pharmacokinetics
PREVACID® (lansoprazole delayed-release capsules)
After oral doses of 14C-lansoprazole in gum arabic suspensions or in gelatin capsules, 27% of the radioactivity was absorbed in mice, 37% in rats, and 63 to 87% in dogs. However, due to degradation and hepatic metabolism of the absorbed dose, bioavailability was much lower, representing 4% in mice and rats and 22% in dogs. Peak levels of parent drug in mice, rats, and dogs were reached within 2 hours after dosing, and plasma concentrations generally increased with dose size. Considerable interanimal variability was found in monkeys, and Cmax values occurred from 0.5 to 6 hours after a 50 mg/kg oral dose in gum arabic. Following an oral dose of lansoprazole, AUC values ranged from 10 to 1230 ng•h/mL in mice (1.5 to 50 mg/kg), 30 to 9639 ng•h/mL in rats (2 to 150 mg/kg), 450 to 8800 ng•h/mL in dogs (0.5 to 50 mg/kg), and 4750 ± 4990 ng•h/mL in monkeys (50 mg/kg). The half-life of lansoprazole ranged from 0.2 to 1.2 hours in mice and rats and had a tendency to increase with dose size; the half-life in dogs averaged 0.6 to 1.7 hours, and in monkeys was 3.3 hours. The AUC and Cmax parameters were reasonably consistent after multiple doses of lansoprazole in mice and rats, were variable in monkeys, and decreased appreciably in dogs. The pharmacokinetic data for lansoprazole is summarized in Table 15. For pharmacokinetic parameters of lansoprazole in humans, see ACTION AND CLINICAL PHARMACOLOGY. Following oral or intravenous administration of a 2 mg/kg dose of racemic lansoprazole to rats and dogs, Cmax and/or AUC values were about 2- to 3-fold greater for the (+) enantiomer than the (-) enantiomer. In vitro studies with racemic lansoprazole and the individual isomers using rat and dog liver 9000 x g supernatants suggested that the (-) isomer is metabolized more rapidly than the (+) isomer, resulting in lower plasma concentrations of the (-) isomer. Both enantiomers apparently inhibit acid secretion to about the same extent.
Circulating metabolites in rats and dogs included the sulfide (M-I), benzimidazole (M-III), the 5-hydroxysulfide (M-IV), 5-hydroxylansoprazole (M-VI), the sulfone (M-VII), the 5-hydroxysulfone (M-IX) and the hydroxymethyl metabolite (M-X), (see Figure 1). Pharmacokinetic characterization of these metabolites has not been done. However, studies of total uncharacterized metabolites have demonstrated that, based on Cmax values after oral doses, the plasma levels exceed those of parent drug by 1.3 to 19 fold in mice, rats, and dogs. The half-life of the metabolites averaged 1 to 3 hours in mice, and 8 to 11 hours in rats and dogs.
Table 15. Summary of Pharmacokinetic, Metabolism and Excretion Data for Lansoprazole in Animals
Parameter
| Mouse | Rat |
Dog
Oral Doses (mg/kg)
| (1.5 – 50) | (2 – 150) |
(0.5 – 50)
Plasma
Lansoprazole
Cmax (ng/mL)
| 30 to 1840 | 10 to 2872 |
350 to 3470
Tmax (h)
| 0.17 to 0.34 | 0.25 to 2 |
0.25 to 2 t1/2 (h)
| 0.2 to 1.1 | 0.3 to 1.2 |
0.6 to 1.7
AUC (ng•h/mL)
| 10 to 1230 | 30 to 9639 |
450 to 8800
Metabolites
Cmax (ng/mL)
| 210 to 15600 | 140 to 4290 |
450 to 7490
Tmax (h)
| 0.17 to 0.34 | 0.5 to 1 |
1 to 2 t1/2 (h)
| 1.4 to 3.1 | 8 to 11.9 |
7.9 to 11.1
AUC (ng•h/mL)
| 260 to 17370 | 1130 to 38100 |
4410 to 62700
Excretion
Urine (% Dose)
| 17.9 |
12 to 24.6
Feces (% Dose)
| 81.0 |
67.5 to 83.7
Bile (% Dose)
| 59.6 |
42.6
Metabolism
Urine (%Dose)
Lansoprazole
| 0.1 | |||
0 to 0.1
M-II to M-V
| 1.4 to 1.9 | |||
0.2 to 1.5
M-VI to M-IX
| 0.2 to 1.3 | |||
0.2 to 1.3
M-X
| 3.6 | |||
1.3
Feces (%Dose)
Lansoprazole
| 0.8 | |||
0 to 1.2
M-I, M-III
| 0.7 to 1.0 | |||
0.7 to 1.5
M-II
| 8.7 | |||
0 to 14.8
M-IV
| 18.5 | |||
14.9 to 33.4
M-V to M-X
| 0.6 to 1.7 | |||
0.7 to 3.5
Bile (%Dose)
Lansoprazole
| 0.2 | |||
M-I to M-III
| 0.1 to 1.5 | |||
M-IV
| 10.7 | |||
6.0
M-V, M-VII, M-VIII
| 0.6 to 1.0 | |||
M-VI
| 1.8 | |||
8.0
M-IX
| 4.1 | |||
3.7
Metabolites M-I through M-X are identified in Figure 1.
Protein Binding
Lansoprazole was extensively bound to plasma proteins. At lansoprazole concentrations ranging from 10 to 5000 ng/mL, protein binding ranged from 92 to 96% in rat and dog plasma. Binding of the drug to mouse plasma proteins has not been studied.
Distribution and Accumulation
The distribution and accumulation of lansoprazole in tissues have been studied in rats, and one accumulation study was done in mice. No tissue distribution studies have been reported in dogs. Lansoprazole was rapidly distributed throughout the body of rats after a 2 mg/kg oral dose, with relatively high concentrations in the intestine, stomach, liver, kidney, and thyroid. Tissue to plasma ratios of 2 to 35 were noted in these tissues. Concentrations in the brain and all other tissues examined were lower than circulating levels. After multiple oral doses (2 mg/kg/day) for 7 days, radioactivity in plasma and tissues was slightly elevated, and the overall distribution patterns were similar. The cumulative excretion curves parallelled the administered dose, suggesting little accumulation of the drug in tissues with daily dosing. In both the single- and multiple-dose studies, most of the drug was cleared from all tissues except the thyroid after 72 hours. The tissue distribution pattern in mice 24 hours after a single, oral 1.5 mg/kg dose was comparable to that seen in rats. Accumulation of the dose in plasma and practically all tissues of mice and rats were observed after large oral doses of 50 mg/kg/day for 26 days.
Lansoprazole readily penetrated into the parietal cells of the gastric mucosa of rats and persisted for 24 hours. Levels of parent drug in the mucosa were 2- to 5-fold greater than those in plasma up to 6 hours after a 2 mg/kg intravenous dose, supporting the concept that lansoprazole suppresses acid secretion by inhibiting the (H+, K+)-ATPase enzyme located in these cells.
Enzyme Induction and Inhibition
Daily, oral administration of a 150 mg/kg dose of lansoprazole to rats for 5 days resulted in a moderate induction of microsomal, mixed function oxidase enzymes in the liver. Microsomal protein, total cytochrome P450, and cytochrome b5 levels were increased 12 to 45%, while activities of p-nitroanisole O-demethylase and p-nitrophenyl glucuronyltransferase were elevated about 2- to 3-fold. Moreover, incubation of lansoprazole with rat liver microsomes (60 to 1500 mcg/g liver) inhibited the in vitro metabolism of aminopyrine, aniline, and p-nitroanisole from 8 to 71%. The data suggested that acute doses may inhibit some drug-metabolizing enzymes, while chronic doses induce their formation.
Metabolic Pathways
In vitro studies demonstrated that lansoprazole was preferentially metabolized by the liver in rats, but metabolic activity was also found in whole blood, kidney, and especially rat fecal contents. The drug is acid labile, and intestinal degradation has also been reported. A total of 10 metabolites (designated as M-I to M-X) have been identified in biologic samples from rats and dogs. Many of the metabolites were found as sulfate or glucuronic acid conjugates. The metabolic scheme is illustrated in Figure 1.
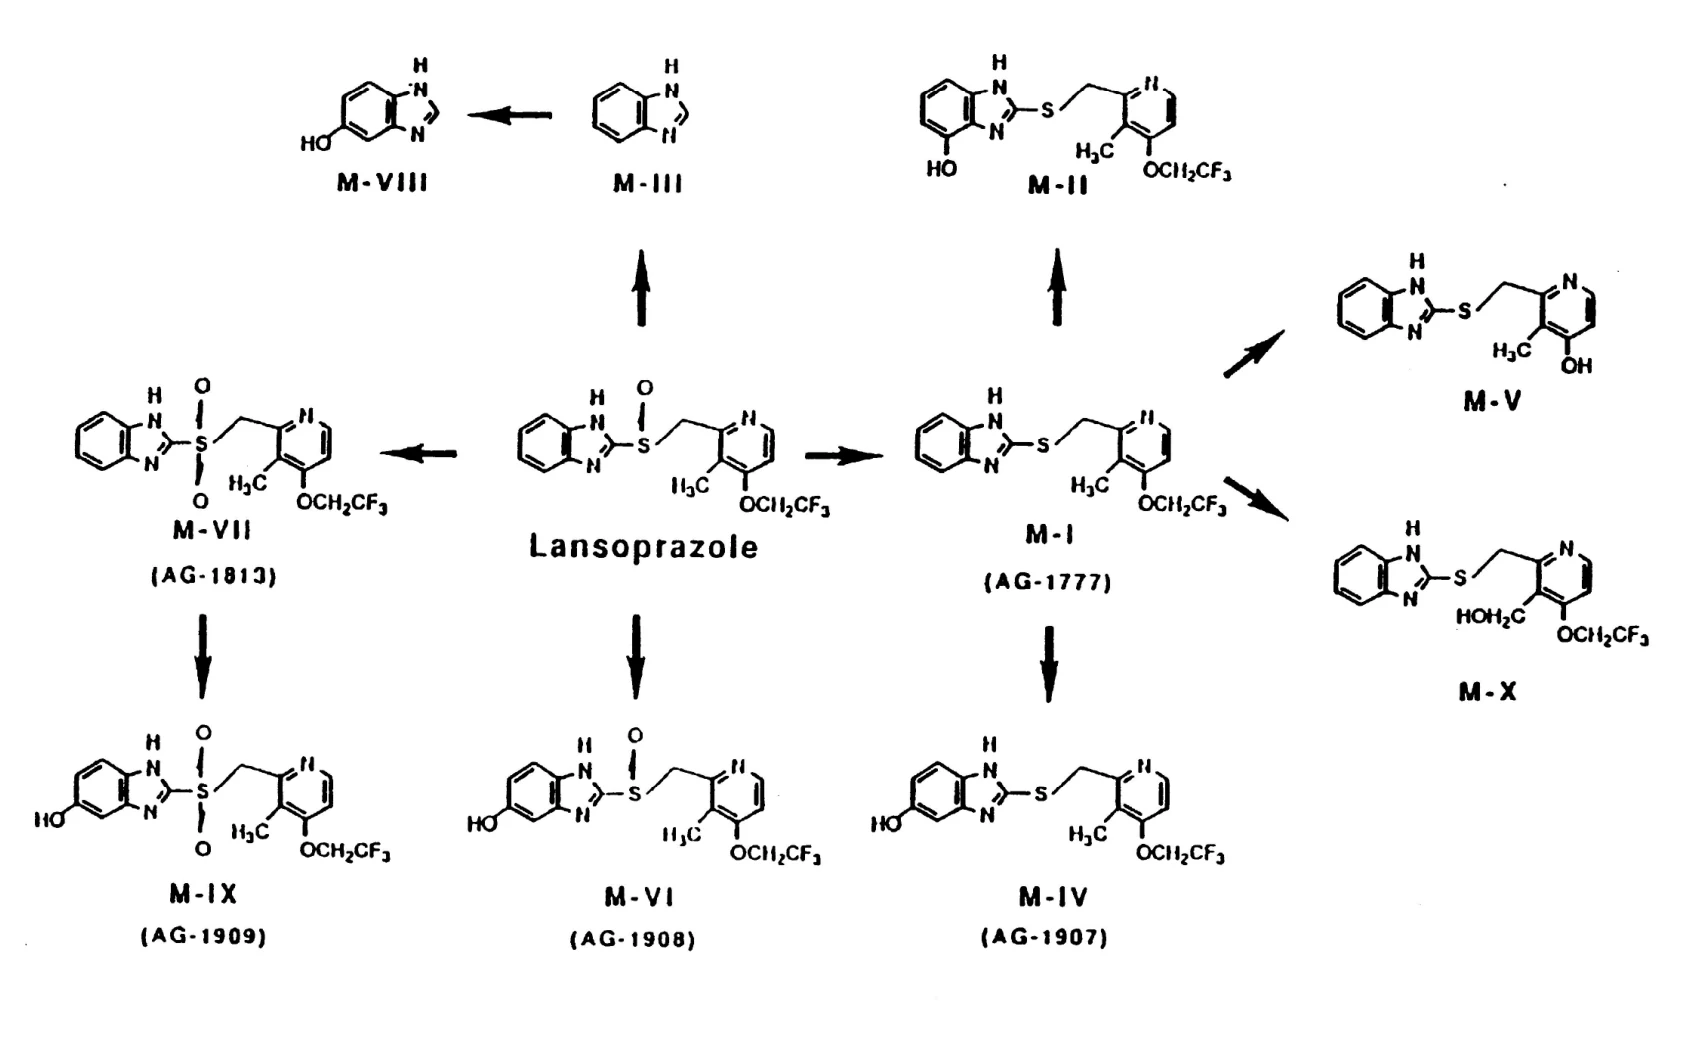
Figure 1. Postulated Metabolic Pathway of Lansoprazole in Rats and Dogs
Lansoprazole is metabolized by the following pathways: 1) reduction and oxidation of the sulfoxide group to form the sulfide (M-I) and sulfone (M-VII); 2) hydroxylation on the benzimidazole ring to give 6-hydroxysulfide (M-II), 5-hydroxysulfide (M-IV), 5-hydroxylansoprazole (M-VI), 5-hydroxybenzimidazole (M-VIII), and 5-hydroxysulfone (M-IX);
- 3) hydroxylation of the methyl group on the pyridine ring (M-X); 4) dealkylation (M-V); and
- 5) elimination of the pyridylmethylsulfinyl group to form benzimidazole (M-III).
Excretion
Both urinary and fecal excretions were involved in eliminating lansoprazole and its metabolites from the body. About 12 to 25% of the dose was found in the urine, while 68 to 84% was excreted into the feces, primarily via the bile. Metabolites M-II through M-X (free and conjugated) were found in the urine of rats and dogs and represented 0.2 to 3.6% of the dose. The sulfide (M-I) and free parent drug were not detected in urine.
Unchanged lansoprazole was a minor fecal component (approximately 1% of the dose), while the major metabolites were identified as the free 5-hydroxysulfide (M-IV) and the 4-hydroxysulfide (M-II), representing about 15 to 33 and 9 to 15% of the dose in rats and dogs, respectively. The remaining 8 metabolites were also detected, and each accounted for 0.6 to 3.5% of the dose, but about half of the metabolites were not characterized. Metabolite profiles in rat bile showed that, except for the hydroxymethyl metabolite (M-X), all other identified metabolites were present. The 5-hydroxysulfide (M-IV), 5-hydroxylansoprazole (M-VI) and the 5-hydroxysulfone (M-IX) were major components of rat and dog bile, representing 6 to 11, 2 to 8, and 4% of the dose, respectively. As noted in the feces, many of the biliary metabolites have not been characterized. Excretion Data for lansoprazole are summarized in Table 16.
Table 16. Excretion Data for the Lansoprazole Dose in Animals and Humans
Species
Dose (mg/kg) | Route |
Percent of the Carbon-14 Dose
| Urine | Feces |
Bile
Rat
2 2-D 2 | oral oral intraduodenal | 17.9 16.7 13.2 | 81.0 81.5 20.8 |
59.6
Dog
2 0.5 0.5 0.5 | oral oral intravenous intravenous | 12 24.6* 28.4* | 83.7 67.5 63.9 |
42.6
Human
| ca. 0.43 | oral | 32.2 | 64.3 |
* Includes cagewash Definitions: D = daily dosing
Humans
PREVACID® (lansoprazole delayed-release capsules)
Mechanism of action
Lansoprazole belongs to a class of antisecretory compounds, the substituted benzimidazoles, that do not exhibit anticholinergic or histamine H2 antagonist properties, but that suppress gastric acid secretion by specific inhibition of the (H+,K+)-ATPase enzyme system at the secretory surface of the gastric parietal cell. Because this enzyme system is regarded as the acid (proton) pump within the parietal cell, lansoprazole has been characterized as a gastric acid-pump inhibitor, in that it blocks the final step of acid production. This effect is dose-related and leads to inhibition of both basal and stimulated gastric acid secretion irrespective of the stimulus. The inhibition of gastric acid secretion persists for up to 36 hours after a single dose. Thus, the plasma elimination half-life of lansoprazole does not reflect its duration of suppression of gastric acid secretion.
Antisecretory activity
After oral administration, lansoprazole was shown to significantly decrease the basal acid output, and significantly increase the mean gastric pH and percent of time the gastric pH was > 3 and > 4. Lansoprazole also significantly reduced meal-stimulated gastric acid output and secretion volume. Lansoprazole also significantly reduced pentagastrin-stimulated acid output. In patients with hyper secretion of acid, lansoprazole significantly reduced basal and pentagastrin-stimulated gastric acid secretion. Lansoprazole inhibited the normal increases in secretion volume, acidity and acid output induced by insulin.
In a crossover study comparing lansoprazole 15 and 30 mg to omeprazole 20 mg for 5 days, the following effects of lansoprazole on intragastric pH were noted (Table 17).
Table 17. Mean Antisecretory Effects of Lansoprazole After Multiple Daily Dosing
Parameter
| Baseline Value | Lansoprazole 15 mg | Lansoprazole 30 mg |
Omeprazole
20 mg
Mean 24-hour pH
| 2.05 | 4.03† | 4.91* |
4.16† Mean Nighttime pH
| 1.91 | 3.01† | 3.80* |
3.04† % Time Gastric pH > 3
| 18 | 59† | 72* |
61† % Time Gastric pH > 4
| 12 | 49† | 66* |
51†
Note: An intragastric pH of > 4 reflects a reduction in gastric acid by 99%.
* (p < 0.05) versus baseline, lansoprazole 15 mg and omeprazole 20 mg.
† (p < 0.05) versus baseline only.
After the initial dose in this study, increased gastric pH was seen within 1 to 2 hours with lansoprazole 30 mg, 2 to 3 hours with lansoprazole 15 mg, and 3 to 4 hours with omeprazole 20 mg. After multiple daily dosing, increased gastric pH was seen within the first hour
postdosing with lansoprazole 30 mg and within 1 to 2 hours postdosing with lansoprazole 15 mg and omeprazole 20 mg.
Higher levels of acid suppression have been predicted to potentiate the activity of antibiotics in eradicating H. pylori. The percentage of time gastric pH was elevated above 5 and 6 was evaluated in a crossover study of PREVACID® (lansoprazole delayed-release capsules) given once daily, twice daily and three times a day (Table 18).
Table 18. Mean Antisecretory Effects After 5 Days of Twice Daily and Three Times Daily Dosing of
Lansoprazole
Parameter
| 30 mg once daily | 15 mg twice daily | 30 mg twice daily |
30 mg three times daily
% Time Gastric pH > 5
| 43 | 47 | 59+ |
77*
% Time Gastric pH > 6
| 20 | 23 | 28 |
45*
+ (p < 0.05) versus Lansoprazole 30 mg once daily
* (p < 0.05) versus Lansoprazole 30 mg once daily, 15 mg twice daily and 30 mg twice daily
The inhibition of gastric acid secretion as measured by intragastric pH returns gradually to normal over 2 to 4 days after multiple doses. There is no indication of rebound gastric acidity.
Other gastric and esophageal effects
Lansoprazole did not significantly affect mucosal blood flow in the fundus of the stomach. Due to the normal, physiologic effect caused by the inhibition of gastric acid secretion, a decrease of 17% in blood flow in the antrum, pylorus and duodenal bulb was seen. Lansoprazole did not significantly affect gastric emptying of liquids, but significantly slowed the gastric emptying of digestible solids. Esophageal motility and lower esophageal sphincter tone were not modified by lansoprazole therapy. Lansoprazole increased serum pepsinogen levels and decreased pepsin activity under basal conditions and in response to meal stimulation or insulin injection. In patients with gastric ulcer, increases in gastric pH were associated with increases in nitrate-reducing bacteria and elevation of nitrite concentration in gastric juice; however no significant increase in nitrosamine concentrations were observed.
Enterochromaffin-like cell effects / Carcinoid formation
In two 24-month carcinogenicity studies, Sprague-Dawley rats were treated orally with doses of 5 to 150 mg/kg/day about 1 to 40 times the exposure on a body surface (mg/m2) basis of a 50 kg person of average height (1.46 m2 body surface area) given the recommended human dose of 30 mg/day (22.2 mg/m2). Lansoprazole produced dose-related gastric enterochromaffin-like (ECL) cell hyperplasia and ECL cell carcinoids in both male and female rats. It also increased the incidence of intestinal metaplasia of the gastric epithelium in both sexes. In male rats lansoprazole produced a dose related increase of testicular interstitial cell adenomas. The incidence of these adenomas in rats receiving doses of 15 to 150 mg/kg/day (4 to 40 times the recommended human dose based on body surface area) exceeded the low background incidence (range = 1.4 to 10%) for this strain of rats. Testicular interstitial cell adenoma also occurred in 1
of 30 rats treated with 50 mg/kg/day (13 times the recommended human dose based on body surface area) in a one year toxicity study. Hypergastrinemia secondary to prolonged and sustained hypochlorhydria, such as that induced by high doses of ranitidine, omeprazole, and surgery, has been postulated to be the mechanism by which ECL cell hyperplasia and gastric carcinoid tumors develop.
Gastric biopsy specimens from the body of the stomach from over 300 patients treated continuously with lansoprazole for 8 weeks to 120 weeks have not shown evidence of ECL effects similar to those seen in rats. Longer term data are needed to rule out the possibility of an increased risk for the development of gastric carcinoid tumors in patients receiving long-term therapy with lansoprazole.
Serum gastrin effects
Fasting serum gastrin levels increased modestly during the first 2 to 4 weeks of therapy with 15 to 60 mg of lansoprazole. This increase was dose-dependent. Median serum gastrin values in over 2100 patients treated with lansoprazole 15 to 60 mg remained within normal range and generally increased 1.5 to 2 fold. Gastrin values returned to pretreatment levels within 4 weeks after discontinuation of therapy.
Endocrine effects
Human studies for up to 1 year have not detected any clinically significant effects on the endocrine system. Hormones studied included testosterone, luteinizing hormone (LH), follicle stimulating hormone (FSH), sex hormone binding globulin (SHBG), dehydroepiandrosterone sulphate (DHEA-S), prolactin, cortisol, estradiol, insulin, aldosterone, parathormone, glucagon, thyroid stimulating hormone (TSH), triiodothyronine (T3), thyroxine (T4), and somatotropic hormone (STH). Lansoprazole in oral doses of 15 to 60 mg for up to 1 year had no clinically significant effect on sexual function. In addition, lansoprazole in oral doses of 15 to 60 mg for 2 to 8 weeks had no clinically significant effect on thyroid function.
In 24-month carcinogenicity studies in Sprague-Dawley rats with daily dosages up to 150 mg/kg, proliferative changes in the Leydig cells of the testes, including benign neoplasm, were increased compared to control rats. These findings are rat specific.
Other effects
No systemic effects of lansoprazole on the central nervous system, lymphoid, hematopoietic, renal, hepatic, cardiovascular or respiratory systems have been found in humans. Lansoprazole in oral doses of 15 to 60 mg for 2 to 8 weeks had no clinically significant effect on thyroid function. No PREVACID®-related visual adverse events were noted in over 7000 patients treated in Phase I to Phase III clinical trials worldwide. No visual toxicity was observed among 63 patients who had extensive baseline eye evaluations, were treated with up to 180 mg/day of lansoprazole and were observed for up to 68 months. Other rat-specific findings after a lifetime exposure included focal pancreatic atrophy, diffuse lymphoid hyperplasia in the thymus, and spontaneous retinal atrophy.
BIAXIN BID® (clarithromycin tablets, USP, film-coated)
Helicobacter pylori
The presence of H. pylori may damage the mucosal integrity and defenses so that exposure to acid/pepsin, even in normal concentrations, produces ulceration.
H. pylori displays potent urease activity which may produce an alkaline environment around the organism. Excess ammonia produced by urea hydrolysis is toxic to mucosal cells and may lead to parietal cell failure and/or to a disturbance of the normal negative feedback of acid to the antral G-cells which secrete gastrin. In addition, H. pylori produces catalases, lipases, phospholipases, proteases, adhesins and toxins. These enzymes may further degrade the mucous layer and damage the epithelial cell membrane. Also, the presence of H. pylori stimulates an active inflammatory response which contributes to mucosal damage.
Gustavson et al. (1995) showed that concentrations of 39.3, 23.1 mcg/g and 25.2 mcg/g clarithromycin were achieved in the gastric mucosa 2, 4, and 6 hours respectively after administering 500 mg clarithromycin t.i.d. and that corresponding concentrations of the 14 hydroxy-metabolite were 3.2, 1.1, and 4.1 mcg/g respectively. Similar results were obtained whether or not clarithromycin was given alone or together with 40 mg omeprazole once daily (Logan et al., 1995). Although the activity of the hydroxy metabolite is about half of the parent drug and its concentrations are lower, it may still contribute antibacterial activity.
AMOXICILLIN (amoxicillin trihydrate) Capsules
Amoxicillin is stable in the presence of gastric acid. Amoxicillin is rapidly and well absorbed after oral administration to fasting subjects. It was found in a recent study that peak serum antibiotic levels were reduced by 50% in subjects receiving amoxicillin immediately following a standard meal. Reducing the dose–water volume given with amoxicillin from 250 to 25 mL in fasted subjects also caused a significant reduction in serum amoxicillin levels. This may be due to the low water solubility of amoxicillin trihydrate (1000 mg in 370 mL water). In addition, food ingestion immediately before dosing also reduced the urinary excretion.
Peak serum levels are attained between 1 and 2 hours after drug administration. Amoxicillin diffuses readily into most body tissues and fluids, with the exception of brain and spinal fluid. Amoxicillin is excreted largely unchanged in the urine while 10 to 25% of the administered dose is excreted in the form of penicilloic acid. The excretion of amoxicillin can be delayed by concurrent administration of probenecid. Amoxicillin is not highly protein bound. In blood serum, amoxicillin is approximately 17 to 18% protein bound compared to 59% for penicillin G.
The following amoxicillin mean serum levels were found following the administration of 250 mg capsules of Amoxicillin to 12 healthy adult volunteers:
| Time (h) | 0.5 | 1 | 1.5 | 2 | 3 | 4 | 5 | 7 |
| Mean Serum Levels (mcg/mL) | 0.81 | 2.96 | 3.17 | 3.1 | 2.22 | 1.12 | 0.5 | 0.11 |
Peak blood serum levels averaged 3.8 mcg/mL (range 2.35 to 6.38 mcg/mL) and the Tmax was 1.50 hours. The mean biological half-life (t½) was found to be 55.8 minutes with a mean elimination rate constant Kel of 0.7456 hour-1.
Twelve normal male subjects participated in a bioavailability study of Amoxicillin Granules for Suspension. Each subject was given 5 mL (250 mg) of reconstituted Amoxicillin Granules for Suspension in a single dose.
The following amoxicillin mean serum levels were found:
| Time (h) | 0.5 | 1 | 1.5 | 2 | 3 | 4 | 5 | 7 |
| Mean Serum Levels (mcg/mL) | 3.26 | 4.19 | 3.4 | 2.56 | 1.65 | 0.98 | 0.43 | 0.1 |
Peak plasma concentrations from 2.65 to 5.75 mcg/mL were obtained with a mean Cmax of 4.24 ± 0.74 mcg/mL. The time required to reach peak concentrations ranged from 0.5 to 1.5 hours, with a Tmax mean of 1.00 ± 0.21 hour.
The AUC's calculated for 0 to 7 hours ranged from 8.475 to 12.865 mcg•h/mL. The mean AUC was 10.713 ± 1.443 mcg•h/mL. The mean biological half-life for Amoxicillin Granules for Suspension was 26.4 minutes. The mean elimination rate constant (Kel) was 1.57 hour-1.
The administration of 500 mg amoxicillin to healthy fasting subjects has been reported to produce peak mean serum levels of 10.8 mcg/mL and 6.75 mcg/mL. Additional studies in healthy volunteers with normal renal function receiving 500 mg doses, indicated that peak serum levels could vary from 5.0 to 10.8 mcg/mL. Serum amoxicillin half-life values reported in the literature vary from 1 to 1.3 hours. About 60 to 80% of an oral dose of amoxicillin is excreted in the urine. In the presence of renal impairment the serum half-life increases (between 7 and 10 hours), necessitating a reduction in the dosage administered.
MICROBIOLOGY
BIAXIN BID® (clarithromycin tablets, USP, film-coated)
Clarithromycin exerts its antimicrobial action by binding to the 50S ribosomal subunit of susceptible microorganisms resulting in inhibition of protein synthesis.
Clarithromycin is active in vitro against various aerobic and anaerobic gram-positive and gram-negative organisms. Additionally, the 14-OH clarithromycin metabolite also has significant antimicrobial activity which may be additive to the activity of the parent compound.
Clarithromycin is bactericidal to Helicobacter pylori; this activity is greater at neutral pH than at acid pH.
In vitro Activity of Clarithromycin against Helicobacter pylori
Clarithromycin has demonstrated in vitro activity against H. pylori isolated from patients with duodenal ulcers. In vitro susceptibility testing methods (broth microdilution, agar dilution, E-test, and disk diffusion) and diagnostic products currently available for determining MICs and zone sizes have not been standardized, validated, or approved for testing H. pylori. The clarithromycin MIC values and zone sizes will vary depending on the susceptibility testing methodology employed, media, growth additives, pH, inoculum concentration tested, growth phase, incubation atmosphere, and time.
Susceptibility Test for Helicobacter pylori
In vitro susceptibility testing methods and diagnostic products currently available for determining MICs and zone sizes have not been standardized, validated, or approved for testing H. pylori microorganisms. MIC values for H. pylori isolates collected during 2 U.S. clinical trials evaluating clarithromycin plus omeprazole, were determined by broth microdilution MIC methodology (Hachem CY et al., 1996). Results obtained during the clarithromycin plus omeprazole clinical trials fell into a distinct bimodal distribution of susceptible and resistant clarithromycin MICs.
If the broth microdilution MIC methodology published in Hachem CY et al., 1996 is used and the following tentative breakpoints are employed, there should be reasonable correlation between MIC results and clinical and microbiological outcomes for patients treated with clarithromycin plus omeprazole (see Table 19).
Table 19. Susceptibility Testing for H. pylori in Patients Treated With Clarithromycin and
Omeprazole
MIC (mcg/mL) Interpretation
≤ 0.06 Susceptible (S)
0.12 to 2.0 Intermediate (I)
≥ 4 Resistant (R)
These breakpoints should not be used to interpret results obtained using alternative methods.
TOXICOLOGY
PREVACID® (lansoprazole delayed-release capsules)
Acute Toxicity
Mouse and Rat
In an acute toxicity study, lansoprazole administered via the oral, subcutaneous and intraperitoneal routes was studied in groups of 5M, 5F Wistar rats and 5M, 5F ICR mice. Lansoprazole was suspended in 5% gum arabic adjusted to pH 7 for administration by all 3 routes. The LD50 by the oral route in both rats and mice was greater than 5000 mg/kg, the highest dose tested. There were no deaths in either study. The only clinical sign noted was dark brown urine in mice.
By the subcutaneous route, the LD50 was again greater than 5000 mg/kg, the highest dose tested. Again, there were no deaths in either species. Scratching at the injection site and abdominal stretching were observed in mice. There were no clinical signs in rats. Drug remnants were seen at the injection sites in both species.
Finally, when lansoprazole was administered via the intraperitoneal route, there were no deaths in mice at 5000 mg, but several rats of both sexes died within 2 days after dosing. Surviving rats were normal by the second day after dosing. The LD50 in rats was approximately 5000 mg. Abdominal stretching, decreases in activity, respiratory depression, and hypotonia of abdominal muscles were seen in rats and mice. Dark purple urine was also seen in mice. At autopsy, drug remnants were seen in the peritoneal cavity in animals of both species. Discoloration of the liver was also seen in rats that died at 5000 mg. These studies demonstrated that lansoprazole has a very low degree of toxicity when given as a single dose by either the oral, subcutaneous, or intraperitoneal routes.
In an acute toxicity study of several metabolites, a contaminant, and partially degraded lansoprazole (40°C and 75% relative humidity for 6 months) were determined in ICR mice. The compounds and the routes tested were pyridyl-oxide derivative (oral), sulfonyl derivative or metabolite VII (oral and intraperitoneal), thio derivative or metabolite I (oral and intraperitoneal), 5-hydroxy derivative or metabolite VI (intraperitoneal), and partially degraded lansoprazole (oral). There were no deaths, and the LD50 values in all cases were therefore greater than 5 g/kg, the limit dose. With oral administration, clinical signs were seen only with partially degraded lansoprazole. These included decreased activity, respiratory depression, hypo-irritability (decreased responsiveness), ataxia, and flattened posture (prostration). With intraperitoneal administration, decreased activity, hypo-irritability, and respiratory depression were seen with metabolites VI and VII. In addition, with metabolite VII, chromaturia (dark purple urine) and soft feces or diarrhea were seen. These findings are all similar to the results of previous acute toxicity studies with lansoprazole. Therefore, none of the tested compounds were more toxic than lansoprazole itself.
Dog
In a single-dose study, 2 male beagle dogs per group (fasted for 18 hours) were given lansoprazole orally by gavage at doses of 500, 1000, and 2000 mg/kg. The drug was suspended in 5% gum arabic, pH 7. The dogs were observed for 15 days after dosing and subjected to necropsy. Organ weights and histopathologic assessments of selected organs were obtained. There were no deaths, no treatment- related clinical signs, no effects on body weight or food consumption, no effects on weights of major organs, and no treatment-related gross or histopathologic changes. Therefore, a single dose of 2000 mg/kg was non-toxic. Higher dosing was not justified for humane reasons.
Long-Term Toxicity
Mouse
In a 3-month study, lansoprazole was given by oral gavage to groups of 10 male and 10 female CD-1 mice at dosages of 0, 15, 50, and 150 mg/kg/day. The vehicle was 5% gum arabic. Clinical signs, body weight, and food consumption were monitored. At the end of the study, blood was collected for hematology and biochemistry measurements. All animals were necropsied. Histologic evaluations were conducted on high-dosage and control animals, and stomachs were evaluated histologically in all animals
There were no treatment-related deaths and no effects on clinical signs, body weight, food consumption, hematology, or serum chemistry variables. There were no treatment-related gross pathologic changes. Stomach weights were increased, and hyperplasia/hypertrophy of the glandular stomach was seen histologically at 50 and 150 mg/kg/day. These changes were secondary to the pharmacologic activity of the compound.
In a 13-week study, lansoprazole was given by oral gavage to groups of 10 male and 10 female CD-1 mice at dosages of 0, 150, 300, 600, 1200, and 2400 mg/kg/day. The drug was suspended in 5% gum arabic, pH 7. There were 3 possibly drug-related deaths at 2400 mg/kg/day. The only clinical sign observed was purple urine seen in all drug-treated groups. There were slight decreases (approximately 10 to 13% relative to controls) in hematocrit, hemoglobin, and erythrocyte counts in all drug-treated groups. Neutrophils were slightly decreased in drug-treated females. Total serum protein was decreased at 300 mg/kg/day or more. Stomach weights were increased in all drug-treated groups. Liver weights were increased at 300 mg/kg/day or more. Testis weights were decreased at 1200 and 2400 mg/kg/ day. At necropsy, the glandular stomach appeared thickened, and erosions of the mucosa were evident at all dosages. The testes appeared small at 1200 and 2400 mg/kg/day. Histologically, hyperplasia and vacuolation were seen in the gastric fundic mucosa in all drug-treated groups. A mild, chronic gastritis was seen at 300 mg/kg/day or more. Hepatocellular hypertrophy and vacuolation were seen at 150 mg/kg/day or more, and a brown pigment was seen in the liver mainly at 2400 mg/kg/day. Seminiferous tubular atrophy and aspermatogenesis were seen with increased incidence at 1200 and 2400 mg/kg/day. Reduced amount of sperm was seen in the epididymides at 1200 mg/kg/day or more. A no-toxic-effect dosage was not determined in this study. The maximum therapeutic dose was judged to be in the range of 300 to 600 mg/kg/day.
Rat
In a 3-month study, lansoprazole was administered by gavage to groups of 15 Sprague-Dawley rats/sex at dosages of 0, 5, 15, 50, and 150 mg/kg/day 7 days per week. The drug was suspended in 5% gum arabic, pH 7.
There were no deaths and no behavioural signs of toxicity. Body weight was decreased in males at 150 mg/kg/day. There was no effect on food consumption. Hemoglobin and mean cell hemoglobin were decreased in females at 50 mg/kg/day or more, and in males at 150 mg/kg/day. Hematocrit was also decreased in males and females, and mean erythrocyte volume was decreased in males at 150 mg/kg/ day. Total leukocyte counts were increased in females at 50 mg/kg/day or more. Serum total protein and globulin were decreased and A/G ratio increased in males at 150 mg/kg/day. There were no gross lesions noted at necropsy. Stomach weight was increased at 15 mg/kg/day or more. Liver weights were increased in females at 15 mg/kg/day or more. Thyroid and uterus weights were increased at 150 mg/kg/day. Thymus weights were decreased at 50 mg/kg/day or more. Histologically, thymic atrophy was observed at 15 mg/kg/day or more. In the stomach, increased chief cell hypertrophy, eosinophilia and single cell necrosis, eosinophilic material in gastric glands, and increased squamous cell hyperplasia and hyperkeratosis at the junction of the glandular and non-glandular mucosa were observed at 50 mg/kg/day or more.
Toxicity was demonstrated by decreased body weight in males, hematologic changes, decreases in serum protein, thymic atrophy, and chief cell necrosis. Hematologic changes and chief cell necrosis occurred at 50 mg/kg/day or more. Thymic atrophy was observed at 15 mg/kg/day or more. Therefore, the no-toxic-effect dosage was 5 mg/kg/day.
In a 4-week study, lansoprazole was administered orally by gavage to 10 Wistar rats/sex/group at dosages of 0, 15, 50, and 150 mg/kg/day (7 days/week). The drug was suspended in 5% gum arabic for administration.
There were no deaths and no behavioural signs of toxicity. Body weight gain was suppressed in males by 7% at 50 mg/kg/day and by 15% at 150 mg/kg/day. Food consumption was decreased in both sexes at 150 mg/kg/day and in males at 50 mg/kg/day. Hepatic drug-metabolizing enzymes, aminopyrine-N-demethylase and aniline hydroxylase activities, were increased at 150 mg/kg/day. Thymic atrophy was noted at necropsy at 150 mg/kg/day. Thymic weights were decreased 21 to 27% at 50 mg/kg/day and 48 to 49% at 150 mg/kg/day. Liver weights were increased at 50 and 150 mg/kg/day. Adrenal weights were increased in females at 150 mg/kg/day. Histologically, centrilobular hepatocellular hypertrophy was seen in the liver at 150 mg/kg/day. An increase in smooth endoplasmic reticulum in the liver was seen by electron microscopy. In the stomach, vacuolation of parietal cells and apical eosinophilia of chief cells were seen histologically, while dilation of parietal cell tubulovesicles was seen by electron microscopy at 150 mg/kg/day.
Toxicity was demonstrated by decreases in body weight gain and food consumption, and thymic atrophy at 50 mg/kg/day or more. The no-toxic-effect dosage was 15 mg/kg/day.
In a 13-week study, lansoprazole was administered to Wistar rats (10/sex/group) at dosages of 0, 5, 15, and 50 mg/kg/day, 7 days/week. The drug was suspended in 5% gum arabic adjusted to pH 7.
There were no deaths and no behavioral signs of toxicity. Body weight was decreased 5 to 6% in both sexes by the end of the study at 50 mg/kg/day. There were no treatment-related effects on hematology, serum chemistry, or urinalysis variables. Measurements of plasma T3, T4, and TSH in the high-dosage and control animals revealed no differences between the 2 groups. Statistically significant elevations in serum gastrin, determined 20 hours post-dosing at the end of the study, were obtained in females at 15 mg/kg/day or more and in males at 50 mg/kg/day. At necropsy, the stomach glandular mucosa was observed to be thickened in both sexes at 50 mg/kg/day and in females at 15 mg/kg/day. Stomach weights were increased at all dosages.
Thymus and submaxillary weights were decreased at 50 mg/kg/day. Histologically, centrilobular hepatocellular hypertrophy was seen in the liver at 50 mg/kg/day. In the stomach, increased argyrophil cell density, hypertrophy of parietal cells, and sporadic necrosis of chief cells were seen at 50 mg/kg/day. Chief cell eosinophilia, hypertrophy, and hyperplasia were seen at all dosages. Dilation of tubulovesicles in parietal cells and small, dense granules in chief cells were seen by electron microscopy at 50 mg/kg/day.
Toxicity was demonstrated by decreased body and thymus weights and chief cell necrosis at 50 mg/kg/day. The no-toxic-effect dosage was 15 mg/kg/day.
In a 13-week study, male Wistar rats were given daily dosages of 50 mg/kg/day lansoprazole orally by gavage, and were then allowed to recover without treatment for periods of 4, 13, or 26 weeks. A control group was given vehicle (5% gum arabic, pH 7). There were 10 rats for each of the necropsy intervals (13 weeks treatment, 4 weeks recovery, 13 weeks recovery, and 26 weeks recovery).
The changes observed at the end of 13 weeks of treatment were similar to those seen at 50 mg/kg/day in the previous 13-week study. In this study, gastrin-secreting cells (G cells) were determined in the stomach pylorus by immunohistochemical staining. The volume density of G cells was found to be increased after 13 weeks of treatment. All of the changes were found to be reversible after 4 weeks recovery without treatment except stomach weight, changes in chief cells, and the increase in argyrophil cells. The increase in argyrophil cells was reversible after 13 weeks of recovery. Necrosis, eosinophilia, hypertrophy, and hyperplasia of chief cells showed partial reversal after 4 and 13 weeks recovery and complete reversal after 26 weeks, recovery. Stomach weight in the treated group was comparable to controls after 26 weeks of recovery.
In a 6-month study, lansoprazole was given to Sprague-Dawley rats (12/sex/group) at dosages of 0, 2, 10, and 50 mg/kg/day, 7 days/week. The drug was suspended in 5% gum arabic, pH 7, and administered orally by gavage.
There were no treatment-related deaths, no behavioral signs of toxicity, no effects on body weight or food consumption, and no treatment-related changes in serum chemistry or urinalysis variables. There was a transient decrease in hematocrit, mean erythrocyte cell volume, and mean
erythrocyte cell hemoglobin at 50 mg/kg/ day after 3 months of treatment. This was not seen at the end of the study. Stomach weight was increased in females at all dosages and in males at 10 mg/kg/ day or more. Thymus weights were decreased at 50 mg/kg/day. Histologically, thymic atrophy was seen at 10 mg/kg/day or more. In the stomach, increased hypertrophy, eosinophilia, and single cell necrosis of chief cells and an increase in argyrophil cells were seen at 10 mg/kg/day or more. At 50 mg/kg/day, dilation of gastric glands and increased severity of inflammatory cell accumulation, squamous cell hyperplasia, and hyperkeratosis at the junction of the glandular and nonglandular mucosa were seen.
Toxicity was demonstrated by the hematologic changes at 50 mg/kg/day, thymic atrophy at 10 mg/kg/day or more and chief cell necrosis at 10 mg/kg/day or more. The no-toxic-effect dosage was 2 mg/kg/day.
In a 1-year study, lansoprazole was administered by oral gavage to Sprague-Dawley rats (30/sex/group) at dosages of 0, 1.5, 5, 15, and 50 mg/kg/day, 7 days per week. The vehicle was 5% gum arabic adjusted to pH 7.
There were no treatment-related deaths and no behavioral signs of toxicity. Body weight gain was decreased in males at 50 mg/kg/day, but there was no effect on food consumption. Hematocrit and hemoglobin were decreased at 50 mg/kg/day. There were no treatment-induced changes in serum chemistry or urinalysis variables. Stomach weight was increased at 5 mg/kg/day or higher. Liver weight was increased in females, while thymus weight was decreased in males at 50 mg/kg/day. Histologic evidence of thymic atrophy was also seen at 50 mg/kg/day. In the stomach, hypertrophy, eosinophilia and necrosis of chief cells was seen at 5 mg/kg/ day or more. Dilated gastric glands and increased incidence of argyrophil cells were seen at 15 mg/kg/day or more. Increased severity of inflammatory cells, squamous hyperplasia, and hyperkeratosis at the junction of the glandular and nonglandular mucosa was seen at 50 mg/kg/day. In the testis at 50 mg/kg/day, an increased incidence of Leydig (interstitial) cell hyperplasia was observed, and a single, benign Leydig cell tumor was found.
Toxicity was characterized by decreased body weight gain in males, decreases in hematocrit and hemoglobin, thymic atrophy, and Leydig cell hyperplasia at 50 mg/kg/day and by chief cell necrosis at 5 mg/kg/day or more. The no-toxic- effect dosage was 1.5 mg/kg/day.
Dog
In a 6-month study, lansoprazole was given to 4 beagle dogs/sex/group in hard gelatin capsules at dosages of 0, 2, 10, and 50 mg/kg/day 7 days per week.
There were no deaths or behavioral signs of toxicity. There were no treatment- related effects on body weight, food consumption, urinalysis, or ophthalmologic, electrocardiographic, or serum chemistry variables. One dog in the high-dosage group had a few atrioventricular (A-V) nodal escape beats; however, this sometimes occurs spontaneously in dogs and was not considered treatment related either by the sponsor or a consulting veterinary cardiologist. There were transient (present at at 3 months but not at six months) decreases in hematocrit, hemoglobin, and erythrocyte counts in males at 2 and 10 mg/kg/day. Hematocrit, hemoglobin, mean cell
hemoglobin, and mean erythrocyte volume were persistently decreased at both 3 and 6 months at 50 mg/kg/day in males. Total leukocyte count was increased in females at 50 mg/kg/day. There were no treatment-related findings at necropsy. Thymus weight was decreased in males at 50 mg/kg/day. Histologically, increased vacuolation of parietal cells in the gastric mucosa was seen at 10 mg/ kg/day or more.
Toxicity was characterized by hematologic changes and by decreased thymus weights at 50 mg/kg/day. The no-toxic effect dosage was 10 mg/kg/day.
In a 12-month study, Beagle dogs were given lansoprazole in hard gelatin capsules at dosages of 0, 1.5, 5, 15, and 50 mg/kg/day, 7 days per week. There were 4 dogs/sex/group. There were 2 deaths, 1 male each at 15 and 50 mg/kg/day.
In surviving dogs, there were no behavioral signs of toxicity, no effects on body weight or food consumption, no treatment-related ophthalmoscopic findings, and no effects on serum chemistry or urinalysis variables. There were no electrocardiogram (ECG) abnormalities in any of the dogs in the study. Total leukocyte counts were increased at 15 and 50 mg/kg/day; the increase at 15 mg/kg/day was transient (present at 3 months but not at later intervals) and in males only. Prostate weight was decreased at 5 mg/kg/day or more. Histologically, increased parietal cell vacuolization was seen at all dosages.
The cause of death or moribundity could not be determined for the 2 dogs that died. There were no indications from the other dogs in the study of any toxicity that could account for these deaths. Nevertheless, a conservative approach suggests that these 2 deaths be considered the result of toxicity due to drug treatment. Therefore, the no-toxic-effect dosage for this study was 5 mg/kg/day.
Pediatric Rat and Dog Studies
Two studies were conducted to evaluate the toxicity and toxicokinetics of lansoprazole in preadolescent rats and dogs. Selected dosages for the 2 species were identical to those used in adult animals in 4-week (Wistar strain) and 13-week (Sprague Dawley strain) studies in rats (Atkinson and Daly, 1986; Miyajima, 1986) and in a 13-week study in dogs (Chiba, 1989; Miyajima, 1989). Dosing of rats continued between weaning throughout adolescence (i.e., reproductive maturity). This age-range simulated the children age group of 2- to 12-year-olds. In dogs, dosing started 2 weeks after birth and continued for 4 weeks prior to weaning, followed by 7 weeks post-weaning for a total of 13 weeks. Evaluation of the stomach was emphasized, since part of the rationale for these studies was to evaluate the threshold for toxicity in target organ(s), particularly the stomach in younger premature animals and compare it to that of adult animals.
These studies also aimed at verifying any additional effects on developmental milestones due to dosing at these young ages.
The toxicity profile in preadolescent animals was not different from adult animals, and the no observable effect level (NOEL) doses were comparable between the 2 age groups. In the pediatric population the mean total initial lansoprazole dose is 0.87 mg/kg. Accordingly, the
safety margin based on the NOEL of 5 mg/kg/day in 2 species was approximately 1- to 1.5-fold, based on plasma levels for lansoprazole only (excluding its metabolites); was approximately 1- to 3.5-fold based on surface area and was about 5.7- fold relative to this clinical dose.
Juvenile Animal Toxicity Data
In a juvenile rat study, adverse effects on bone growth and development and heart valves were observed at lansoprazole doses higher than the maximum recommended equivalent human dose.
An eight-week oral toxicity study with a four-week recovery phase was conducted in juvenile rats with lansoprazole administered from postnatal Day 7 (age equivalent to neonatal humans) through 62 (age equivalent to approximately 14 years in humans) at doses of 40 to 500 mg/kg/day (about 1.2 to 12 times the daily pediatric dose of 15 mg in children age one to 11 years weighing 30 kg or less, based on AUC).
Heart valve thickening occurred at a lansoprazole dose of 500 mg/kg/day (approximately 12 times the daily dose of 15 mg in pediatric patiensts based on AUC, age one to 11 years weighing 30 kg or less). Heart valve thickening was not observed at the next lower dose (250 mg/kg/day) and below. The findings trended towards reversibility after a four-week drug-free recovery period.
No effects on heart valves were observed in a 13-week intravenous toxicity study of lansoprazole in adolescent rats (approximately 12 years human age equivalence) at systemic exposures similar to those achieved in the eight-week oral toxicity study in juvenile (neonatal) rats.
In the eight-week oral toxicity study of lansoprazole, doses equal to or greater than 100 mg/kg/day produced delayed growth, with impairment of weight gain observed as early as postnatal Day 10 (age equivalent to neonatal humans). At the end of treatment, the signs of impaired growth at 100 mg/kg/day and higher included reductions in body weight (14% to 44% compared to controls), absolute weight of multiple organs, femur weight, femur length and crown-rump length. Femoral growth plate thickness was reduced only in males and only at the 500 mg/kg/day dose. The effects related to delayed growth persisted through the end of the 4-week recovery period. Longer term data were not collected.
In a follow-up developmental sensitivity toxicity study, juvenile rats (12 rats per treatment group) were orally administered 250 and/or 500 mg/kg/day lansoprazole for four or eight weeks starting on postnatal Day (PND) 7 (age equivalent to neonatal humans), PND 14 (age equivalent to approximately one year in humans), or PND 21 (age equivalent to approximately two years in humans).
Signs of toxicity (lower mean body weight gain and/or heart valve thickening) were observed in all dose groups of juvenile rats. Incidences of heart valve thickening were 2/12, 5/12 and 0/12, respectively, in juvenile rats in those groups dosed starting at ages 7, 14, and 21 day with 500 mg/kg/day lansoprazole for 4 weeks. Heart valve thickening in animals in those groups dosed with 500 mg/kg/day lansoprazole for eight weeks starting at PND 7, 14, and 21 were 2/12, 7/12, and 1/12, respectively.
Due to the high incidence of mortality (9 of 24 males were found dead and 15 of 24 males were euthanized between PND 18 and PND 21) in the 500 mg/kg/day dose group starting at PND 14, the 500 mg/kg/day dose groups were terminated and replaced with 250 mg/kg/day dose groups.
Incidences of heart valve thickening in juvenile rats dosed with 250 mg/kg/day (approximately four times the expected lansoprazole exposure based on AUC in pediatric patients 1 to 11 years of age) starting at PND 14 were two (2/12) and one (1/12) in the four week and eight week dose groups, respectively. Incidences of the heart valve thickening were observed in almost all dose groups. Juvenile rats younger than PND 21 (age equivalent to approximately two years in humans) were more sensitive to the development of heart valve thickening.
The relevance of these findings to pediatric patients less than 12 years of age is unknown. The findings in this study are not relevant for patients 12 years of age and above.
BIAXIN BID® (clarithromycin tablets, USP, film-coated)
Acute Toxicity
The acute toxicity of clarithromycin administered by a variety of routes, was studied in mice and rats. The median lethal dose by the oral route ranged from 2.7 to > 5.0 g/kg. Acute toxicity did not differ markedly between sexes (see Table 20).
Table 20. Acute LD50 values of Clarithromycin
Species
| Sec | Route | ||
LD50 value (g/kg)
Mice
| Male | oral oral subcutaneous subcutaneous intraperitoneal intraperitoneal intravenous intravenous | ||
| Female | |||
| Male | |||
| Female | |||
| Male | |||
| Female | |||
| Male | |||
| Female |
2.74
2.7
> 5.0
> 5.0
1.03
0.85
0.17
0.2
Rats
| Male | oral oral subcutaneous subcutaneous intraperitoneal intraperitoneal | ||
| Female | |||
| Male | |||
| Female | |||
| Male | |||
| Female |
3.47
2.7
> 5.0
> 5.0
6.69
7.58
The primary signs of toxicity included reduction in activities, behaviours, weight gains, respiration rates and sedation. The emetic activity of clarithromycin prevented the determination of the lethal dose in dog.
The acute oral toxicity of clarithromycin in very young mice and rats was determined. The median lethal dose (1.2 g/kg) was about 2 fold that seen in the older rodents.
Subchronic Toxicity
Studies were conducted in rats, dogs and monkeys with clarithromycin administered orally. The duration of administration ranged from 14 days to 42 days.
Rats
One study in rats (with oral doses up to 800 mg/kg/day) failed to show adverse effects in rats exposed to 50 mg/kg/day for 4 weeks. The clinical signs observed at toxic doses were reduced motility, piloerection, hypothermia and perineal urine staining. Changes occurred in biochemical
parameters at 200 and 800 mg/kg/day indicative of hepatotoxicity which was confirmed by histopathologic findings of hepatocyte necrosis.
Other pathologic findings at the top 2 dose levels included swelling of the renal cortical tubular epithelia and atrophic changes to the lymphatic and genital systems. The same toxicity profile was observed in immature rats following the daily administration of oral doses up to 150 mg/kg/day of clarithromycin for 6 weeks. At 150 mg/kg/day, there was an increase in relative weights of liver and kidneys.
Dogs
Dogs were dosed orally with 0, 6.25, 25, 100 or 400 mg/kg/day of clarithromycin daily for 28 days. Emesis occurred sporadically in the treated dogs. No other adverse effects were seen in dogs exposed to 6.25 mg/kg/day. The clinical signs at higher dosages included loose stools, lacrimation and conjunctivitis.
Slight anorexia was noted in dogs receiving 100 mg/kg/day or more. Dogs at 400 mg/kg/day exhibited reduced red blood cell count, hematocrit, hemoglobin concentration, serum albumin, and mean urine pH and specific gravity. Increases were seen in serum transaminase, alkaline phosphatase, and total bilirubin concentrations.
Bilirubin was detected in the urine. Other pathologic changes at 400 mg/kg/day included biliary hyperplasia, gastric glandular atrophy, renal tubule epithelial atrophy, edema of the iris, ciliary body and choroid, capillary proliferation in the cornea, suppression of spermatogenesis, and adrenal medullary degeneration.
Monkeys
Monkeys were treated daily for 1 month with oral doses of 0, 25, 100 or 400 mg/kg/day. Two animals out of 10 receiving 400 mg/kg/day died. Salivation was recorded at all dosage levels. No other adverse effects were seen in animals treated daily with 25 mg/kg/day.
The clinical signs observed at higher doses and most frequently at 400 mg/kg/day were vomiting, emesis, sunken eyes, dehydration, emaciation, low rectal temperature, body weight loss, reduced food consumption, cloudiness of the cornea and reduction in intra-ocular pressure. Yellow discoloured feces were passed on a few isolated occasions by some animals given a dose of 400 mg/kg/day. As with the other species, the liver was the primary target at toxic doses as shown by early elevation of serum concentration of glucose, BUN, creatinine, ALT, AST, LDH, amylase and/or triglyceride; an electrolyte imbalance and low levels of protein, cholesterol, phospholipid; elevated leucine aminopeptidase (LAP).
Principal histopathologic changes were seen mainly in high dose monkeys, but some mid-dose monkeys exhibited similar alterations. Changes included necrosis and vacuolation of hepatocytes, vacuolation of renal cortical tubules, no spermatogenesis, thymic regression and single cell necrosis of the stomach. In man the recommended dose is 500 to 1000 mg/day or 7.1 to 14.3 mg/kg/day (70 kg person).
Chronic Toxicity
Rats
Rats (20/sex/group) were treated daily with oral doses of 0, 15, 37.5, 75 or 150 mg/kg/day for 3 months. There were 8 incidental deaths, but none of them were considered treatment related. Clinical signs included increased salivation, dehydration, hyperactivity and were observed in a dose-related manner. The only toxic effect noted, was some variation in body weight gain. No toxicologically significant changes occurred in hematology, biochemistry or urinalysis results.
Post mortem, there was an increase in mean relative liver and kidney weights at the top dose level. No microscopic changes were detected in the kidneys, but in the liver, there was a sex/dose-related increase in multinucleated hepatocytes. Effects were only seen in females at 150 mg/kg/day but in males occurred as low as 37.5 mg/kg/day.
A 6-month oral study was performed in rats (20 to 27/sex/group) at dosages of 0, 1, 6, 8, 40 or 200 mg/kg/ day. Seven male and female rats from the control group and the 40 and 200 mg/kg/day groups were allowed a 63-day non-dosed recovery period. No mortalities occurred. Body weight and food intake were reduced at high doses during the dosing phase but normalized during recovery.
Water intake and urine volume increased in males and females of the 40 and 200 mg/ kg/day groups. Dose-related hematological changes included reduced erythrocytes and HCT with increased MCV, MCH and MCHC and relative eosinophil counts. Biochemical changes were mainly restricted to the high dose group and included increased ALP and decreased phospholipids; decreased total cholesterol and triglycerides, and increased AST and ALT in males only and decreased albumin in females only.
Organ weight increases were found to include cecum, adrenals, liver, and spleen. Histopathological examinations showed drug-related, recovery-reversible, increases in multinucleated hepatocytes associated with minimal and focal necrosis in livers of both sexes at the top 2 dose levels. No relevant pathology was found in the cecum, adrenals or spleen to account for the increased weights. After recovery only the 200 mg/kg/day group had increased multinucleated hepatocytes.
Dogs
Dogs (7/sex/group) were administered daily with oral doses of 0, 10, 30, or 100 mg/kg/day of clarithromycin for 3 months. Emesis occurred at levels of 30 mg/kg and above. One male high dose dog was killed in extremis on day 69. Drug-related lesions were seen in the liver, gall bladder, thymus and stomach.
Hematological and biochemical changes at the high dose level included, decreased RBC and HCT, increased ALT, ALP, GGT, and decreased total protein and albumin. No significant organ weight changes were recorded, but treatment-related microscopic alterations in the liver and
stomach of mild and high dose dogs were seen, as well as changes in gall bladder, spleen and thymus of high dose animals.
A 6 month oral study was also performed in dogs (4 to 5/sex/group) at dosages of 0, 0.8, 4, 20 or 100 mg/kg/day. At the 0 and 100 mg/kg levels, 1 male and 1 female dog were allowed a 1-month, non-dosed, recovery period. One male high dose dog died on day 174. This death was considered to be as a direct result of clarithromycin administration. Histopathologic examination revealed hepatic parenchymal damage, identifying the cause of clinical jaundice. Clinical signs during the dosing phase of the study were restricted to the top 2 dose levels and included emesis and ocular signs. Food consumption and water intake were reduced at 20 and 100 mg/kg/day.
Hematologic changes at 100 mg/kg were indicative of subclinical anemia. Biochemical alterations at the same level were associated with liver damage. Ocular changes were only apparent at the top dose level.
Increase in the weights of lung, liver, spleen, adrenals and kidneys were found at 100 mg/kg/day. Histopathologic examination of these organs showed degeneration of liver parenchyma, and toxic effects in adrenals. The thymus weight was reduced at 100 mg/kg/day. At the end of the recovery period all findings had regressed or reduced.
Monkeys
Monkeys (5 to 6/sex/group) were similarly administered clarithromycin at levels of 0, 25, 50 or 100 mg/kg/day for 6 months. At the 0 and 100 mg/kg levels, 1 male and 1 female monkey were allowed a 1-month recovery period. One high dose female died in week 25. Inhalation of vomit was considered to be the cause of death. Clinical signs were restricted to a dose-related incidence of emesis and salivation. No treatment-related effects were found in food consumption, ophthalmoscopy or hematology. Weight loss was restricted to 1 high dose female. Minor serum chemistry changes were seen at the 100 mg/kg level, particularly in plasma proteins. Urinalysis revealed a dose-related lowering of pH and SG at 13 weeks only. Organ weight increases in liver, adrenal and kidneys were seen at high doses, but pathology was restricted to minimal liver changes consisting of cytoplasmic rarefaction of centrilobular hepatocytes. All changes were reversed during the recovery period.
AMOXICILLIN (amoxicillin trihydrate) Capsules
Acute Toxicity
The following LD50 values for amoxicillin expressed in mg/kg of body weight have been reported.
Table 21. Acute LD50 Values for Amoxicllin (mg/kg)
Species Route of Administration
| Oral | Intraperitoneal |
Subcutenous
Mouse
| > 10,000 | 4350 |
> 6,000
Rat
| > 8,000 | 4900 |
> 6,000
Dog
| > 3,000 | - |
-
Subacute Toxicity
Rats
In one study, male and female rats were orally administered 500 mg/kg amoxicillin daily for 21 days. With the exception of significantly greater (p < 0.01) BUN values in the female test group compared with controls, there were no toxic effects on the organs, tissues or fluids of the body, nor any adverse effects on food consumption, weight gain, or efficiency of food utilization reported in the study.
Histopathologic evaluation of tissues revealed a minimal degree of fatty change in livers of treated females. However, this finding was not considered a toxic change but related to a possible alteration in the intestinal flora.
Dogs
One male and 1 female dog were dosed orally with 250 mg/kg amoxicillin daily for 14 days. During the period of observation, no deaths occurred, no adverse changes in body weight and no effect on food consumption was found. Laboratory values were found within normal limits. At post-mortem, no gross or microscopic abnormalities were reported and organ weights were within normal limits.
Chronic Toxicity
Rats
In one study, male and female rats were given oral doses of 200, 500 and 2000 mg/kg/day amoxicillin, 6 days a week for 26 weeks. No apparent disturbances in absolute organ weights of either treated male or female animals were noted nor was any histologic evidence of response to treatment observed.
In another study, 3 groups of Sprague-Dawley rats were given oral doses of 200, 500 and 2000 mg/kg of amoxicillin for a test period of 13 to 15 weeks. There were no gross or histologic changes observed in the treated rats that were considered related to the administration of amoxicillin. Some of the intermediate and low-dose groups were shown to exhibit body weight gains lower (males) or slightly higher (females) than those of the control animals.
Dogs
It has been reported that amoxicillin was administered orally at doses of 200, 500 and 2000 mg/kg/day to male and female dogs for a period of 6 months. (Groups consisted of 6 male and 6 female dogs initially, but after 3 months dosing, each group was reduced to 3 dogs).
During the first 6 weeks of treatment, occasional bouts of vomiting, 1 to 4 hours after dosing, were reported in dogs receiving 2000 mg/kg/day and 4 bouts of vomiting were recorded in dogs receiving the intermediate dose of 500 mg/kg/day. Grey coloured feces were seen on very isolated occasions in dogs treated at high and intermediate dose levels only. On 7 occasions it involved dogs receiving the highest dose level (2000 mg/kg/day) and on 3 occasions dogs receiving the intermediate dose level (500 mg/kg/day).
Body weight gains of treated males were reported to be not significantly different from those of controls, but all dosed females increased in weight at a significantly slower rate than did the controls. This factor was reported to be attributable to excessive weight gain in the control animals. Food and water consumption was not affected. No abnormalities of the eyes were observed attributable to amoxicillin.
In a second study 2 groups of Beagle dogs were given oral doses of 500 mg/kg and 200 mg/kg of amoxicillin for 13 weeks. There were no gross or histologic changes reported in the treated dogs that were considered related to the administration of amoxicillin.
Carcinogenesis
PREVACID® (lansoprazole delayed-release capsules)
In two 24-month carcinogenicity studies, Sprague-Dawley rats were treated orally with doses of 5 to 150 mg/kg/day about 1 to 40 times the exposure on a body surface (mg/m2) basis of a 50 kg person of average height (1.46 m2 body surface area) given the recommended human dose of 30 mg/day (22.2 mg/m2). Lansoprazole produced dose-related gastric enterochromaffin-like (ECL) cell hyperplasia and ECL cell carcinoids in both male and female rats. It also increased the incidence of intestinal metaplasia of the gastric epithelium in both sexes. In male rats lansoprazole produced a dose related increase of testicular interstitial cell adenomas. The incidence of these adenomas in rats receiving doses of 15 to 150 mg/kg/day (4 to 40 times the recommended human dose based on body surface area) exceeded the low background incidence (range = 1.4 to 10%) for this strain of rat. Testicular interstitial cell adenoma also occurred in 1 of 30 rats treated with 50 mg/kg/day (13 times the recommended human dose based on body surface area) in a 1-year toxicity study. Testicular Leydig cell hyperplasia and tumors were also
observed. The Leydig cell changes were shown through mechanistic studies to be rat-specific and not biologically relevant to humans.
In a 24-month carcinogenicity study, CD-1 mice were treated orally with doses of 15 to 600 mg/kg/day, 2 to 80 times the recommended human dose based on body surface area. Lansoprazole produced a dose-related increased incidence of gastric ECL cell hyperplasia. Lansoprazole also induced a low, non-dose-related incidence of carcinoid tumours in the gastric mucosa in several dose groups (1 female mouse in the 15 mg/kg/day group, 1 male mouse in the 150 mg/kg/day group, and 2 males and 1 female in the 300 mg/kg/day group). It also produced an increased incidence of liver tumours (hepatocellular adenoma plus carcinoma). The tumour incidences in male mice treated with 300 and 600 mg/kg/day (40 to 80 times the recommended human dose based on body surface area) and female mice treated with 150 to 600 mg/kg/day (20 to 80 times the recommended human dose based on body surface area) exceeded the ranges of background incidences in historical controls for this strain of mice. Lansoprazole treatment produced adenoma of rete testis in male mice receiving 75 to 600 mg/kg/day (10 to 80 times the recommended human dose based on body surface area).
No carcinogenic effect occurred in P53 knockout mice, which are known to be susceptible to carcinogenesis by genotoxic agents.
Analysis of gastric biopsy specimens from patients after short-term treatment of proton pump inhibitors have not detected ECL cell effects similar to those seen in animal studies. Longer term studies in humans revealed a slight increase in the mean ECL-cell density, although there was no microscopic evidence of cell hyperplasia. Similar results were seen in the maintenance treatment studies, where patients received up to 15 months of lansoprazole therapy. Serum gastrin values increased significantly from their baseline values but reached a plateau after 2 months of therapy. By 1 month post-treatment, fasting serum gastrin values returned to lansoprazole therapy baseline. Moreover, results from gastric biopsies from short-term, long-term and maintenance treatment studies indicate that there are no clinically meaningful effects on gastric mucosa morphology among lansoprazole-treated patients.
In a 2-year study, lansoprazole was administered by oral gavage to Sprague-Dawley rats (60 males and 60 females per group) at dosages of 0, 1.5, 5, 15, and 50 mg/kg/day 5 days per week. Drug was suspended in 5% gum arabic (adjusted to pH 7.0 to 7.4).
Survival rates were 27 to 33% in males and 30 to 45% in females. The median survival time was 650 days in males and 683 days in females. Body weight gain was decreased at 50 mg/kg/day in both sexes and at all dosages in females. At the end of the study, body weight gains for high-dose males and females were both decreased 20% compared to controls. There were no other clinical signs of toxicity.
The incidence of interstitial (Leydig) cell hyperplasia was increased above concurrent and historical control levels at dosages of 15 and 50 mg/kg/day. The incidence of Leydig cell tumors was increased above concurrent control levels at 15 mg/kg/day and was at the high end of the historical control range at 50 mg/kg/day. The increases in incidence of Leydig cell hyperplasia and tumors were statistically significant at 15 and 50 mg/kg/day when compared to concurrent
controls. Histologically, the Leydig cell tumors appeared similar to those that occur spontaneously in Sprague-Dawley rats and in aging Fischer 344 rats.
There were numerous changes in the gastric mucosa indicative of the pharmacologic effect of lansoprazole that were similar to those seen in previous toxicity studies. This included necrosis of chief cells which was seen at 5 mg/kg/day or more. A small increase in incidence of intestinal metaplasia was seen in both sexes at 50 mg/kg/day. Detailed examination of the intestinal metaplasia foci revealed the presence of Paneth cells, indicating complete type intestinal metaplasia in virtually every case. A single, carcinoid tumor was seen in the gastric fundic mucosa in a female at 50 mg/kg/day.
The decreases in body weight gain, necrosis of chief cells, and increased incidence of Leydig cell hyperplasia and tumors demonstrated that a MTD was administered.
The results suggest that oral administration of lansoprazole at dosages of 15 and 50 mg/kg/day for 2 years leads to higher levels of interstitial (Leydig) cell hyperplasia and tumors than found in control rats. There was no evidence for any other tumorigenic response due to drug administration.
BIAXIN BID® (clarithromycin tablets, USP, film-coated)
Long-term studies in animals have not been performed to evaluate the carcinogenic potential of clarithromycin.
AMOXICILLIN (amoxicillin trihydrate) Capsules
Long-term studies in animals have not been performed to evaluate the carcinogenic potential of amoxicillin. Studies to detect mutagenic potential of amoxicillin alone have not been conducted.
Mutagenicity
PREVACID® (lansoprazole delayed-release capsules)
Lansoprazole was positive in the Ames assay for bacterial mutagenicity and in the chromosomal aberration studies in human lymphocytes, but it was negative in 3 in vivo studies for genotoxicity. Lansoprazole was not genotoxic in the ex vivo rat hepatocyte unscheduled DNA synthesis (UDS) test, the in vivo mouse micronucleus test, or the rat bone marrow cell chromosomal aberration test. Also, a mammalian cell mutagenesis assay was negative.
In vitro cytogenetics studies showed increased levels of aberrations consisting mainly of chromatid breaks which occurred only at cytotoxic concentrations. These cytotoxic concentrations were at least 50 to 60 times expected clinical blood levels of parent drug. Therefore, such concentrations will not be used in humans.
BIAXIN BID® (clarithromycin tablets, USP, film-coated)
The following in vitro mutagenicity tests have been conducted with clarithromycin: Salmonella/mammalian microsome test, bacterial induced mutation frequency test, in vitro chromosome aberration test, rat hepatocyte DNA synthesis assay, mouse lymphoma assay, mouse dominant lethal study, mouse micronucleus test.
All tests had negative results except the in vitro chromosome aberration test which was weakly positive in 1 test and negative in another. In addition, a Bacterial Reverse-Mutation Test (Ames Test) has been performed on clarithromycin metabolites with negative results.
AMOXICILLIN (amoxicillin trihydrate) Capsules
Long-term studies in animals have not been performed with amoxicillin.
Reproduction and Teratology
PREVACID® (lansoprazole delayed-release capsules)
Six separate studies covering all phases of the reproductive process have been conducted. Treatment with lansoprazole caused a dose related reduction of implantations, viable fetuses and live births, and caused delayed parturition at 150 mg/kg/day.
However, lansoprazole at oral doses up to 150 mg/kg/day (40 times the recommended dose based on body surface area) was found to have no effect on fertility and reproductive performance of male and female rats.
In 2 teratology studies, lansoprazole at dosages up to 300 mg/kg/day (approximately 600 times the human dose) was administered to rats on Days 6 to 17 of pregnancy. At higher dosages (150 to 300 mg/kg/day), only decreased fetal body weights were observed. Also at higher dosages, reduced ossification of vertebrae was indicative of fetal toxicity.
In rabbits, doses of lansoprazole up to 30 mg/kg/day (approximately 60 times the human dose) were administered on Days 6 to 18 of pregnancy. A treatment-related effect on fetal mortality at 30 mg/kg/day was noted, but there were no treatment related external, skeletal, or visceral abnormalities.
Reproductive studies in pregnant rats and rabbits revealed no lansoprazole-related impairment of fertility, fetal malformations or developmental toxicity to fetuses or suckling neonates. Lansoprazole is not considered to be teratogenic.
BIAXIN BID® (clarithromycin tablets, USP, film-coated)
Fertility and reproduction studies have shown that daily doses of 150 to160 mg/kg/day to male and female rats caused no adverse effects on the estrous cycle, fertility, parturition, or number and viability of offspring. Plasma levels in rats after 150 mg/kg/day were 2 times the human serum levels.
In the 150 mg/kg/day monkey studies, plasma levels were 3 times the human serum levels. When given orally after 150 mg/kg/day, clarithromycin was shown to produce embryonic loss in monkeys. This effect has been attributed to marked maternal toxicity of the drug at this high dose.
In rabbits, in utero fetal loss occurred at an intravenous dose of 33 mg/m2, which is 17 times less than the maximum proposed human oral daily dose of 618 mg/m2.
AMOXICILLIN (amoxicillin trihydrate) Capsules
Rats
Daily doses of 200 and 500 mg/kg amoxicillin were administered orally in 1 reported study. Male rats that had attained a minimum age of 40 days were treated for 63 days and sexually mature females for 14 days prior to mating. Dosing continued throughout the remainder of the investigation. The duration of gestation was unaffected by treatment at either dosage. It was noted that pregnancy rate at 500 mg/kg was slightly lower than that of controls at the first and second matings. At 200 mg/kg, the pregnancy rate was essentially comparable to control values at both matings. The chronologic sequence of mating was comparable for all groups; at 500 mg/kg the total number of animals showing evidence of mating was slightly lower than that of controls at both pairings. Pre- and post-implantation losses were comparable for all groups at the first and second pregnancies.
Among the rats allowed to rear their young, litter sizes, litter weights, mean pup weights and the pup mortality rates for the group dosed at 500 mg/kg amoxicillin were comparable to control values at birth, 4 and 21 days postpartum. Mean pup weights and pup mortality rates were similarly unaffected by 200 mg/kg amoxicillin; but litter sizes and litter weights were lower than control values from birth through lactation. These differences were considered to be unrelated to treatment. No abnormal young were observed.
Effects on Pregnancy
Amoxicillin was administered at doses of 200 mg/kg, 500 mg/kg and 1000 mg/kg orally during gestation from day 6 through 15. Amoxicillin did not modify pregnancy, percentage of resorption and did not produce fetal abnormalities as compared with negative control rats.
Effects on Peri- and Post-Natal Development of the Rat
Amoxicillin was administered orally at 200 and 500 mg/kg/day from day 15 of gestation through lactation to 21 days postpartum. Body weight gain, pregnancy rate, and the duration of gestation of parent animals were unaffected by treatment at any dosage. There was a significant dose-related trend to lower litter size and weight at birth. This persisted through lactation to weaning despite reduced pup mortality and increased mean pup weight in the test groups compared with controls. No abnormal young were observed.
Mice
It has been reported that amoxicillin administered at doses of 200, 500 and 2000 mg/kg/day orally during days 6 to 15 of pregnancy produced no obvious signs of reaction to treatment or deaths among parent animals. Body weight changes of pregnant dams were comparable for all groups, as was the pregnancy rate.
Fetal loss was significantly higher among all test groups than among controls. However, as implantation rates also tended to be higher at the 500 and 2000 mg/kg doses, litter sizes were only marginally, and not significantly, lower than the control value. Litter sizes and implantation rate also tended to lie at or above the upper limit of the laboratory range. Due to the latter factors, the biologic importance of the increased fetal loss was uncertain.
It was noted that mean pup weights were comparable for all groups. The distribution of skeletal variants was considered to be unaffected by treatment at any dosage. A significantly higher proportion of pups with cervical ribs was found in the 200 mg/kg dose group. Cervical rib and 14th rib are the prolongations of the transverse processes of the cervical or lumbar vertebrae. Supernumerary ribs have an incidence which depends on the strain of animals. Cervical ribs are not abnormalities and have no pathologic significance.
In this experiment the incidence of cervical ribs was 12% in control rats and 16% in the drug-treated groups if the 3 groups are calculated together. If the groups are considered individually, then in the lowest dose group (200 mg/kg) the incidence of cervical ribs was 24%, which is, statistically, significantly higher than in the controls. This finding was not considered to be drug related since at the 500 mg/kg dose level the incidence of cervical ribs was significantly lower than in controls. At the highest dose level (2000 mg/kg) the incidence of cervical ribs was 17%, similar to the controls. The incidence of visceral abnormalities was not significantly affected at any dose level.
Special Studies
BIAXIN BID® (clarithromycin tablets, USP, film-coated)
Acute Renal Toxicity
There was no evidence of nephrotoxicity of clarithromycin in the rat at doses up to 500 mg/kg/day.
Hepatotoxicity
In the in vitro and in vivo hepatotoxicity studies comparing clarithromycin with erythromycin, it was found that clarithromycin caused no greater cytotoxicity than erythromycin stearate and much less toxicity than erythromycin estolate. Hepatic enzyme induction was not found in doses below 500 mg/kg/day. In cynomolgus monkeys, the closest metabolic model for humans, elevations of ALT and LDH were identified at 200 mg/kg/day.
In dogs, a rise of ALT has been seen at 100 mg/kg/day, and in Wistar rats, a similar elevation of enzymes was seen at 200 mg/kg/day. Morphologic lesions related to prolonged exposure to clarithromycin (up to 6 months) have been consistent with reportedly reversible changes in rat, dog, and monkey studies. Such doses are many times beyond the therapeutic range in humans, which is within 8 to 10 mg/kg/day.
Ocular Toxicity
Ocular lesions appear confined to dogs and monkeys receiving lethal doses, which were large multiples of the human therapeutic dose. Radiolabelled clarithromycin studies indicate the eye is not selectively burdened by drug deposits and that clearance from this tissue follows that seen in other tissues. Opacities occur in the cornea following widespread extraocular tissue changes which are detectable via numerous diagnostic methods. Reduced intraocular pressure precedes corneal opacity in a relatively predictive manner. Some evidence for transient opacity and at least partial resolution was noted in animal studies, but most animals succumbed to other organ dysfunctions shortly after opacities were observed.
Animals given doses close to the therapeutic dose had no ocular changes. No ophthalmologic effects were noted in rabbits treated at doses of 40 and 160 mg/kg/day for 28 days.
Ototoxicity
No effects on pinna reflex were seen in guinea pigs at a dose of 400 mg/kg/day but inner and outer hair cells disappeared suggesting toxic damage. No evidence of damage was reported at 200 mg/kg/day.
PREVACID® (lansoprazole delayed-release capsules)
Retinal Atrophy
In two 24-month toxicology studies in albino rats, drug-related retinal changes were seen at dosages of 15 mg/kg/day or higher in females and 50 mg/kg/day or higher in males. These retinal changes were similar to the spontaneous age-related and/or light induced retinal changes normally seen in rats. However, at the higher dosages, higher incidence of diffuse atrophy involving central as well as peripheral retina and a higher incidence of bilateral retinal atrophy occurred.
Retinal atrophy was only observed in albino rats treated continuously for 2 years. These changes in rats are believed to be associated with the effects of taurine imbalance and phototoxicity in a susceptible animal model. This lesion was not seen in other species including mice dogs and monkeys.
REFERENCES
- 1.
Azuumi Y, Saigenji K. The Mechanism of Action of Proton Pump Inhibitors. Pharma
Medica. 1991;9(6):17-23.
- 2. Bazzoli F, Zagari RM, Fossi S, et al. Efficacy and tolerability of a short-term, low-dose triple therapy for eradication of Helicobacter pylori. Eur J Gastroenterol & Hepatol. 1994;6:773-777
- 3. Béïque L, Giguère P., la Porte C, et al.Interactions between protease inhibitors and acid-reducing agents: a systematic review. HIV Medicine. 2007;8:335-345.
- 4.
Carlsson E. A review of the effects of long-term acid inhibition in animals. Scand J
Gastroenterol. 1989;24(Suppl 166):19-23.
- 5.
Cederbrant G, Schalen C, Kamme C. Clarithromycin combined with its 14-
hydroxymetabolite A-62671 against Helicobacter pylori. University Hospital. Lund, Sweden; Nov 22, 1993.
- 6. Colin-Jones DG. Safety of lansoprazole. Aliment Pharmacol Ther. 1993;7(Suppl. 1):56-60.
- 7.
Cutler AF, Schubert TT. Patient Factors Affecting Helicobacter pylori Eradication with
Triple Therapy. Am J Gastroenterol. 1993;88(4):505-509.
- 8.
DeCross AJ, Marshall BJ. The role of Helicobacter pylori in acid-peptic disease. Am J Med
Sci. 1993;306(6):381-392.
- 9.
Flamm RK, Beyer J, Tanaka SK, Clement, J. Kill kinetics of antimicrobial agents against
Helicobacter pylori. J Antimicrob Chemother. 1996;38:719-725.
- 10. Fukuda Y, Yamamoto I, Okui M, et al. Combination therapies with proton pump inhibitor for Helicobacter pylori-infected gastric ulcer patients. J Clin Gastroenterol. 1995;20(Suppl. 2):S132-135.
- 11. Goddard A, Logan R. One-week low-dose triple therapy: new standards for Helicobacter pylori treatment. Eur. J Gastroenterol & Hepatol. 1995;7:1-3.
- 12. Goldman RC, Zakula D, Flamm R, et al. Tight binding of clarithromycin, its 14(R)-hydroxy metabolite, and erythromycin to Helicobacter pylori ribosomes. Antimicrob Agents Chemother. 1994;38:1496-1500.
- 13. Graham DY, Lew GM, Klein PD et al. Effect of treatment of Helicobacter pylori infection on the long-term recurrence of gastric or duodenal ulcer. Annuls Intern Med. 1992;116:705-708.
- 14. Guay DRP, Craft JC. Overview of the pharmacology of clarithromycin suspension in children and a comparison with that in adults. Pediat Infect Dis J 1993;12(12): S106-111.
- 15. Gustavson LE, Kaiser JF, Edmonds AL et al. Effect of omeprazole on concentrations of clarithromycin in plasma and gastric tissue at steady-state. Antimicrob Agents Chemother. 1995;39:2078-2083.
- 16.
Hachem CY, Clarridge RR, Flamm R, Evans DG, Tanaka SK, Graham DY. Antimicrobial
Susceptibility Testing of Helicobacter pylori. Comparison of E-Test, Broth Microdilution, and Disk Diffusion for Ampicillin, Clarithromycin, and Metronidazole. Diagn Microbiol Infect Dis. 1996;24:37-41.
- 17. Harris AW, Gummett PA, Logan RPH et al. Eradication of Helicobacter pylori with lansoprazole and clarithromycin. Aliment Pharmacol Ther. 1995;9:201-204.
- 18.
Hartzen SH, Andersen LP, Bremmelgaard A, Colding H, et al. Antimicrobial Susceptibility
Testing of 230 Helicobacter pylori Strains: Importance of Medium, Inoculum, and Incubation Time. Antimicrob Agents Chemother. Dec. 1997;41:2634-2639.
- 19. Hazel SL, Lee A, Brady L et al. Campylobacter pyloridis and gastritis: association with intercellular spaces and adaptation to an environment of mucus as important factors in colonization of the gastric epithelium. J Infect Dis. 1986;153:658-663.
- 20.
Kawai T, Ikeda H, Harada Y, Saitou T. Changes in the Rat Stomach after Long-Term
Administration of Proton Pump Inhibitors (AG-1749 and E-3810) Nippon Rinsho. 1992;50(1):188-193.
- 21. Kohli Y, Kato T, Azuma T, Ito S, Hirai M. Lansoprazole treatment of Helicobacter pylori- positive peptic ulcers. J Clin Gastroenterol. 1995;20 (Suppl. 1):S48-S51.
- 22. Lamouliatte H. Adjuvant therapy for Helicobacter pylori eradication: role of lansoprazole in clinical studies. J Clin Gastroenterol. 1995;20 (Suppl. 1): S28-S31.
- 23. Levi S, Beardshall K, Haddad G et al. Campylobacter pylori and duodenal ulcers, the gastrin link. Lancet. 1989;1:1167-1168.
- 24.
Lind T, Velhuyzen van Zanten S, Unge P et al. Eradication of Helicobacter pylori Using
One-Week Triple Therapies Combining Omeprazole with Two Antimicrobials: The MACH I Study. HELICOBACTER; 1996;1(3):138-144.
- 25. Logan RPH, Bardhan KD, Celestin LR et al. Eradication of Helicobacter pylori and prevention of recurrence of duodenal ulcer: a randomized, double-blind, multi-centre trial of omeprazole with or without clarithromycin. Aliment Pharmacol Ther. 1995;9:417-423.
- 26. Nagata K, Satoh H, Iwahi T, Shimoyama T, Tamura T. Potent inhibitory action of the gastric proton pump inhibitor lansoprazole against urease activity of Helicobacter pylori: unique action selective for H. pylori cells. Antimicrob Agents Chemother. 1993(4);37:769-774.
- 27. Parente F, Maconi G, Bargiggia S, Colombo E, Porro G. Comparison of two lansoprazole-antibiotic combinations (amoxicillin or classical triple therapy) for treatment of H. pylori infection in duodenal ulcer patients. Aliment Pharmacol Ther. 1996;10(2):211-213.
- 28.
Sarosiek J, Slomiany A, Slomiany B. Evidence for weakening of gastric mucus integrity by
Campylobacter pylori. Scan J Gastroenterol. 1988;23:585-590.
- 29. Schütze K, Hentschel E. Duodenal ulcer healing after 7-day treatment: a pilot study with lansoprazole, amoxicillin and clarithomycin. Z Gastroenterol. 1995;33(11):651-653.
- 30. Spencer CM, Faulds D. Lansoprazole. A reappraisal of its pharmacodynamic and pharmacokinetic properties, and its therapeutic efficacy in acid-related disorders. Drugs. 1994;48:404-430.
- 31. Spinzi GC, Bierti L, Bortoli A et al. Comparison of omeprazole and lansoprazole in short-term triple therapy for Helicobacter pylori infection. Aliment Pharmacol Ther 1998;12:433-438.
- 32.
Soll AH: Pathogenesis of peptic ulcer and implications for therapy. N Engl J Med.
1990;322:909-916.
- 33.
Soll AH. Gastric, duodenal, and stress ulcer. In: Sleisenger MH, Fordtran JS, eds.
Gastrointestinal disease: pathophysiology/diagnosis/management. 5th edition. Volume 1. Philadelphia: WB Saunders Co., 1993:580-679.
- 34.
Takimoto T, Kenichi I, Taniguchi Y et al. Efficacy of Lansoprazole in Eradication of
Helicobacter pylori. J Clin Gastroenterol. 1995;20 (suppl.2):S121-S124.
- 35.
Tomilo DL et al. Inhibition of Atazanavir Oral Absorption by Lansoprazole Gastric Acid
Suppression in Health Volunteers. Pharmacotherapy 2006;26(3):341-346.
- 36.
Tytgat G. Review article: treatments that impact favourably upon the eradication of
Helicobacter pylori and ulcer recurrence. Aliment Pharmacol Ther. 1994;8(4):359-368.
- 37. Tytgat GNJ, Noach LA, Rauws EAJ. Helicobacter pylori infection and duodenal ulcer disease. Helicobacter pylori Infection. 1993;22:127-139.
- 38. Vakily M, Amer F, Kukulka MJ, Andhivarothai N. Coadministration of lansoprazole and naproxen does not affect the pharmacokinetic profile of methotrexate in adult patients with rheumatoid arthritis. J. Clin Pharmacol. 2005;45(10):1179-1186.
- 39.
Yamamoto I, Fukuda Y, Okui M, Tamura K, Shimoyama T. Proton pump inhibitors for
Helicobacter pylori eradication in patients with peptic ulcer. J Clin Gastroenterol. 1995;20 (Suppl. 1):S38.