


Product Monograph - Irbesartan (Ranbaxy Pharmaceuticals Canada)
ACTION AND CLINICAL PHARMACOLOGY
Irbesartan antagonizes angiotensin II by blocking AT1 receptors.
Angiotensin II is the primary vasoactive hormone in the renin-angiotensin system. Its effects include vasoconstriction and the stimulation of aldosterone secretion by the adrenal cortex.
Irbesartan blocks the vasoconstrictor and aldosterone-secreting effects of angiotensin II by selectively blocking in a non competitive manner the binding of angiotensin II to the AT1 receptor found in many tissues. Irbesartan has no agonist activity at the AT1 receptor. AT2 receptors have been found in many tissues, but to date they have not been associated with cardiovascular homeostasis. Irbesartan has essentially no affinity for the AT2 receptors.
Irbesartan does not inhibit angiotensin converting enzyme, also known as kininase II, the enzyme that converts angiotensin I to angiotensin II and degrades bradykinin, nor does it affect renin or other hormone receptors or ion channels involved in cardiovascular regulation of blood pressure and sodium homeostasis.
Pharmacokinetics
Irbesartan is an orally active agent. The oral absorption of irbesartan is rapid and complete with an average absolute bioavailability of 60% - 80%. Irbesartan exhibits linear pharmacokinetics over the therapeutic dose range with an average terminal elimination half-life of 11-15 hours. Following oral administration, peak plasma concentrations are attained at 1.5-2 hours after dosing. Steady-state concentrations are achieved within 3 days.
Irbesartan is approximately 96% protein-bound in the plasma, primarily to albumin and α1-acid glycoprotein.
The average volume of distribution of irbesartan is 53-93 liters. Total plasma and renal clearances are in the range of 157 - 176 and 3.0 - 3.5 mL/minute, respectively.
Irbesartan is metabolized via glucuronide conjugation, and oxidation by the cytochrome P-450 system. Following either oral or intravenous administration of 14C-labeled irbesartan, more than 80% of the circulating plasma radioactivity is attributable to unchanged irbesartan. The primary
circulating metabolite is the inactive irbesartan glucuronide (approximately 6%). The remaining oxidative metabolites do not add appreciably to the pharmacologic activity.
Irbesartan and its metabolites are excreted by both biliary and renal routes. Following either oral or intravenous administration of 14C-labeled irbesartan, about 20% of radioactivity is recovered in the urine and the remainder in the feces. Less than 2% of the dose is excreted in urine as unchanged irbesartan.
In vitro studies of irbesartan indicate that the oxidation of irbesartan is primarily by cytochrome P-450 isoenzyme CYP 2C9. Metabolism of irbesartan by CYP 3A4 is negligible. Irbesartan is neither metabolized, nor does it substantially induce or inhibit the following isoenzymes: CYP 1A1, 1A2, 2A6, 2B6, 2D6, 2E1. There was no induction or inhibition of CYP 3A4.
In subjects over the age of 65 years, irbesartan elimination half-life was not significantly altered, but AUC and CMAX values were about 20 - 50% greater than those of young subjects.
The mean AUC and CMAX were not altered in patients with any degree of renal impairment, including patients on hemodialysis. However, a wide variance was seen in patients with severe renal impairment.
The pharmacokinetics of irbesartan following repeated oral administration were not significantly affected in patients with mild to moderate cirrhosis of the liver. No data is available in patients with severe liver disease.
Pharmacodynamics
In healthy subjects, single oral doses of irbesartan up to 300 mg produced dose-dependent inhibition of the pressor effect of angiotensin II infusions. The inhibition was complete (100%) 4 hours following oral doses of 150 mg or 300 mg. Partial inhibition of 40% and 60% was still present 24 hours post-dose with 150 mg and 300 mg irbesartan respectively.
In hypertensive patients, angiotensin II receptor inhibition following chronic administration of irbesartan causes a 1.5-2 fold rise in angiotensin II plasma concentration and a 2-3 fold increase in plasma renin levels. Aldosterone plasma concentrations generally decline following irbesartan administration, however serum potassium levels are not significantly affected at recommended doses.
During clinical trials, minimal incremental blood pressure response was observed at doses greater than 300 mg.
The blood pressure lowering effect of irbesartan is apparent after the first dose and substantially present within 1-2 weeks, with the maximal effect occurring by 4-6 weeks. In long-term studies, the effect of irbesartan appeared to be maintained for more than one year. There was essentially no change in average heart rate in patients treated with irbesartan in controlled trials.
There is no rebound effect after withdrawal of irbesartan.
Black hypertensive patients had a smaller blood pressure response to irbesartan monotherapy than caucasians.
CLINICAL TRIALS
COMPARATIVE BIOAVAILABILITY STUDIES
A blinded, balanced, randomized, two-treatment, two-period, two-sequence, single-dose, crossover, bioequivalence study of 1 X 300 mg IRBESARTAN (irbesartan) tablets (Ranbaxy Pharmaceuticals Canada Inc.) and 1 X 300 mg PRAVAPRO® (irbesartan) tablets (Sanofi-Aventis Canada Inc.) was conducted in 24 healthy adult male human subjects under fasting conditions.
Summary Table of the Comparative Bioavailability Data
Irbesartan (1 x 300 mg) From measured data Least Square Geometric Mean Arithmetic Mean (CV %) | ||||
| Parameter | Test* | Reference† | % Ratio of Least Square Geometric Means | 90% Confidence Interval# |
| AUC0-T (ng-hr/mL) | 21504.42 22320.43 (27.9) | 20643.27 21260.38 (25.4) | 104.17 | 97.81-110.95 |
| AUC0-I (ng-hr/mL) | 21930.70 22741.16 (27.6) | 20997.86 21615.66 (25.1) | 104.44 | 98.10-111.19 |
| Cmax (ng/mL) | 3842.58 4013.01(30.1) | 3721.39 3801.67(21.4) | 103.26 | - |
| Tmax^ (h) | 2.00 (0.25 – 4.50) | 2.00 (0.75 – 4.50) | - | - |
| T½ ~ (h) | 9.15 (23.4) | 8.73 (20.7) | - | - |
* IRBESARTAN (irbesartan) 300 mg tablets (Ranbaxy Pharmaceuticals Canada Inc.) †PrAVAPRO® (irbesartan) 300 mg tablets (Sanofi-Aventis Canada Inc.) were purchased in Canada. # Based on least squares estimate.
^Expressed as Median (Range) only
~Expressed as Arithmetic Mean (CV %) only
Two trials were done to investigate the effects of irbesartan in patients with hypertension and type 2 diabetic nephropathy, the IDNT and IRMA 2 trial.
IDNT:
The Irbesartan Diabetic Nephropathy Trial (IDNT) was a multicenter, randomized, controlled, double-blind, morbidity and mortality trial comparing irbesartan, amlodipine and placebo. In 1715 hypertensive patients with type 2 diabetes (proteinuria ≥ 900 mg/day and serum creatinine 1.0 - 3.0 mg/dL) the long-term effects (mean 2.6 years) of irbesartan on the progression of renal
disease and all-cause mortality were examined. In addition, a secondary endpoint, the effect of irbesartan on the risk of fatal or non-fatal cardiovascular events was assessed. Age of onset of Type II diabetes mellitus < 20 years, renovascular occlusive disease affecting both kidneys or a solitary kidney and unstable angina pectoris were among the most important exclusion criteria. Patients were randomized to receive irbesartan 75 mg (n = 579), amlodipine 2.5 mg (n = 567), or matching placebo (n = 569) once-daily. Patients were then titrated to a maintenance dose of 300 mg irbesartan, 10 mg amlodipine, or placebo as tolerated. Additional antihypertensive agents for the three study arms (excluding ACE inhibitors, other angiotensin II receptor antagonists and calcium channel blockers) were added as needed to help achieve a blood pressure goal of 135/85 mmHg or less in all groups, or a 10 mmHg reduction in systolic pressure if baseline was > 160 mmHg. Of the total of 579 patients randomized to irbesartan, 442 completed the double blind phase. All analyses were conducted on the intent to treat (ITT) patient population.
IDNT Primary Endpoint Time to Doubling of Serum Creatinine, ESRD, or Death
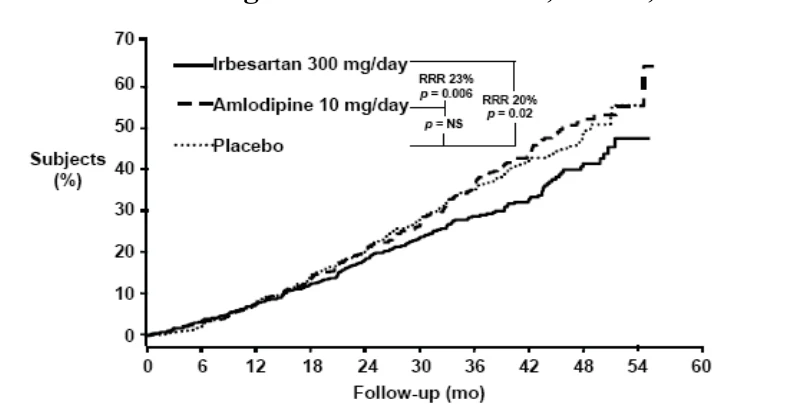
Table 1 Primary Composite Endpoint Comparison (IDNT)
| Number (%) of Subjects | Relative Risk | |||||
| Event | Placebo N=569 | Irbesartan N=579 | Amlodipine N=567 | Estimate (% Reduction) | 95% Confidence Interval | p |
| Irbesartan vs. Placebo | ||||||
| Primary Composite Endpoint* | 222 (39.0) | 189 (32.6) | - | 0.80 (20) | 0.66-0.97 | 0.023 |
| Irbesartan vs. Amlodipine | ||||||
| Primary Composite Endpoint* | - | 189 (32.6) | 233 (41.1) | 0.77 (23) | 0.63-0.93 | 0.006 |
* First occurrence of any of the following: doubling of serum creatinine, end-stage renal disease (ESRD) or all-cause mortality
Irbesartan demonstrated a 20% relative risk reduction (absolute risk reduction 6.4%) in the composite primary endpoint (first occurrence of any of the following: doubling of serum creatinine, end-stage renal disease (ESRD) or all-cause mortality) compared to placebo (p=0.023), and a 23% relative risk reduction (absolute risk reduction 8.5%) compared to amlodipine (p=0.006). When the individual components of the primary composite endpoint were analysed, no effect in all-cause mortality and no significant effect on time to end stage renal
disease were observed. However, a significant reduction was observed in doubling of serum creatinine. Irbesartan decreases the progression of renal disease in patients with chronic renal insufficiency and overt proteinuria. Irbesartan also produced significant reduction in the rate of urine excretion of protein and albumin relative to placebo or amlodipine (p<0.001 for both comparisons). Similar blood pressure was achieved in the irbesartan 300 mg and amlodipine 10 mg groups.
Treatment with irbesartan reduced the occurrence of sustained doubling of serum creatinine as a separate endpoint (33%) with an absolute risk reduction of 6.8%.
The risk of developing a doubling of serum creatinine or ESRD was reduced by 26% relative to placebo with an absolute risk reduction of 6.2% and 34% relative to amlodipine with an absolute risk reduction of 10.0% (pooled risk reduction 30%, p=0.0005). This renal protective effect of irbesartan appears to be independent of systemic blood pressure reduction.
There was no significant difference in the assessment of fatal or non-fatal cardiovascular events (cardiovascular death, non-fatal myocardial infarction, hospitalization for heart failure, permanent neurologic deficit attributed to stroke, or above-the-ankle amputation) among the three treatment groups.
Safety data from this trial has been reported in the ADVERSE REACTIONS section.
IRMA 2:
The study of the Effects of Irbesartan on MicroAlbuminuria in Hypertensive Patients with Type 2 Diabetes Mellitus (IRMA 2) was a multicenter, randomized, placebo-controlled, double-blind morbidity study, conducted in 590 hypertensive patients with type 2 diabetes, microalbuminuria (20-200 mcg/min; 30-300mg/day) and normal renal function (serum creatinine ≤ 1.5 mg/dL in males and ≤ 1.1 mg/dL in females). Screening of urine for albumin has revealed that patients with microalbuminuria have a 10 to 20 fold higher risk of developing diabetic nephropathy than patients with normoalbuminuria. Of the 590 patients, 201 received placebo, 195 received irbesartan 150 mg and 194 patients received irbesartan 300 mg.
The study examined as a primary endpoint the long-term effects (2 years) of irbesartan on the progression to clinical (overt) proteinuria (urinary albumin excretion rate [AER] > 200 mcg/min [>300mg/day] and an increase in AER of at least 30% from baseline). In addition, after one and two years of treatment, the effect of irbesartan on the change in overnight AER and the change in 24-hour creatinine clearance was assessed. Age of onset of Type II diabetes mellitus < 20 years, renovascular occlusive disease affecting both kidneys or a solitary kidney and unstable angina pectoris were among the most important exclusion criteria.
Irbesartan 300 mg demonstrated a 70% relative risk reduction (absolute risk reduction 9.8%) in the development of clinical (overt) proteinuria compared to placebo (p=0.0004). Relative risk reduction in the development of proteinuria with 150 mg irbesartan was not statistically significant. The slowing of progression to clinical (overt) proteinuria was evident as early as three months and continued over the 2 year period.
IRMA 2 Primary Endpoint Time to Overt Proteinuria
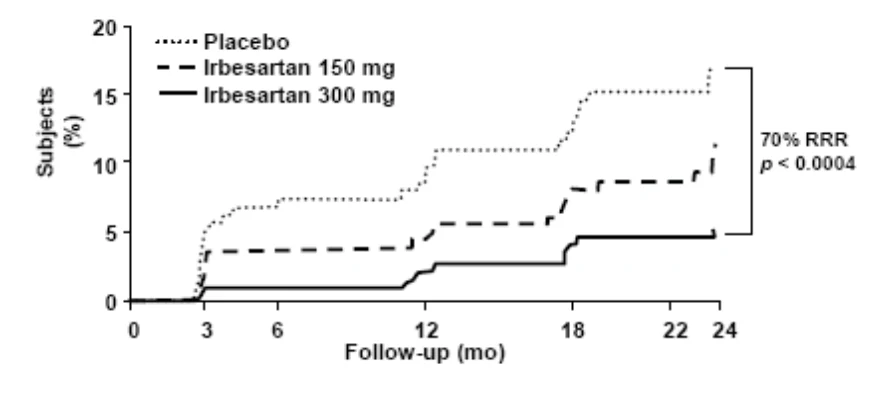
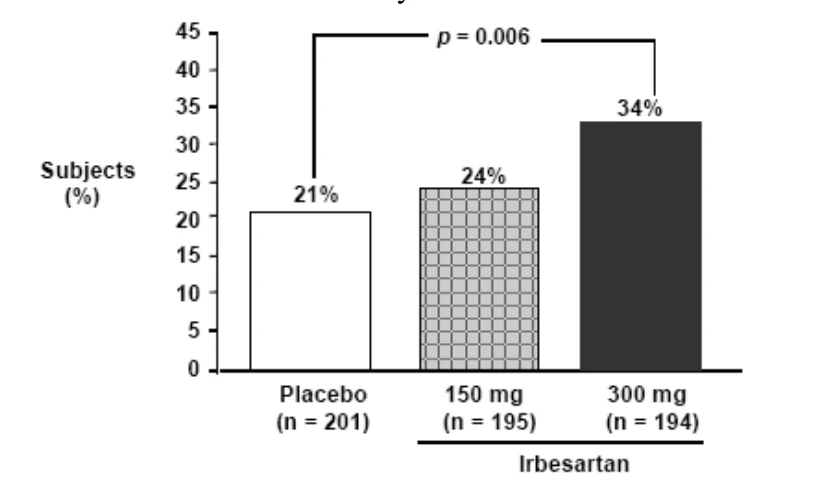
Table 2 Time to occurrence of Overt Proteinuria (Irbesartan 300 mg vs. Placebo Comparison) (IRMA 2)
| Event | Number (%) of Subjects | Relative Risk | |||
| Placebo N=201 | Irbesartan N=195 | Estimate (% Reduction) | 95% Confidence Interval | p | |
| Primary Endpoint | 30 (14.9) | 10 (5.2) | 0.295 (70) | 0.144 - 0.606 | 0.0004 |
Regression to normoalbuminuria (<20 mcg/min; <30 mg/day) was more frequent in the irbesartan 300 mg group (34%) than in the placebo group (21%). Irbesartan 300 mg reduced the level of urinary albumin excretion at 24 months by 43% (p=0.0001).
IRMA 2
Normalization of Urinary Albumin Excretion Rate
Safety data from this trial has been reported in the ADVERSE REACTIONS section.
INDICATIONS AND CLINICAL USE
IRBESARTAN (Irbesartan Tablets USP) is indicated for the treatment of essential hypertension.
IRBESARTAN is also indicated for the treatment of hypertensive patients with type 2 diabetes mellitus and renal disease to reduce the rate of progression of nephropathy as measured by the reduction of microalbuminuria, and the occurrence of doubling of serum creatinine. (See Clinical Trials).
IRBESARTAN may be used alone or concomitantly with thiazide diuretics.
The safety and efficacy of concurrent use with angiotensin converting enzyme inhibitors has not been established.
CONTRAINDICATIONS
IRBESARTAN (irbesartan) is contraindicated in patients who are hypersensitive to any component of this product.
WARNINGS
Serious Warnings and Precautions
When used in pregnancy, angiotensin receptor (AT1) blockers (ARB) can cause injury or even death of the developing fetus. When pregnancy is detected, IRBESARTAN (irbesartan) should be discontinued as soon as possible (see WARNINGS AND PRECAUTIONS, Special Populations).
Special Populations
Pregnant Women
Drugs that act directly on the rennin-angiotensin system (RAAS) can cause fetal and neonatal morbidity and death when administered to pregnant women. When pregnancy is detected, IRBESARTAN (irbesartan) should be discontinued as soon as possible.
The use of ARB is not recommended during pregnancy. Epidemiological evidence regarding the risk of teratogenicity following exposure to angiotensin converting enzyme inhibitors (another class of therapeutic products interfering with the RAAS) during the first trimester of pregnancy has not been conclusive; however a small increase in risk cannot be excluded. Given the current evidence available on the risk with ARB, similar risks may exist for this class of drugs. Patients planning pregnancy should be changed to alternative anti-hypertensive treatments which have an established safety profile for use in pregnancy. When pregnancy is diagnosed, treatment with angiotensin II antagonists should be stopped immediately, and, if appropriate, alternative therapy should be started.
The use of ARBs during the second and third trimesters is known to induce human fetotoxicity (decreased renal function, oligohydramnios, skull ossification, retardation) and neonatal toxicity (renal failure, hypotension, hyperkalaemia).
Infants with histories of in utero exposure to an ARBs should be closely observed for hypotension, oliguria, and hyperkalemia. If oliguria occurs, attention should be directed toward support of blood pressure and renal perfusion. Exchange transfusion may be required as means of reversing hypotension and/or substituting for impaired renal function; however, limited experience with those procedures has not been associated with significant clinical benefit. Irbesartan is not removed by hemodialysis.
Nursing Women
It is not known whether irbesartan is excreted in human milk, but significant levels have been found in the milk of lactating rats. Because many drugs are excreted in human milk, and because of their potential for affecting the nursing infant adversely, a decision should be made whether to discontinue nursing or discontinue the drug, taking into account the importance of the drug to the mother.
Hypotension - Volume Depleted Patients
Occasionally, symptomatic hypotension has occurred after administration of irbesartan, in some cases after the first dose. It is more likely to occur in patients who are volume depleted by diuretic therapy, dietary salt restriction, dialysis, diarrhea, or vomiting. In these patients, because of the potential fall in blood pressure, therapy should be started under close medical supervision (see DOSAGE AND ADMINISTRATION). Similar considerations apply to patients with ischemic heart or cerebrovascular disease, in whom an excessive fall in blood pressure could result in myocardial infarction or cerebrovascular accident.
PRECAUTIONS
Renal Impairment
As a consequence of inhibiting the renin-angiotensin-aldosterone system, changes in renal function have been seen in susceptible individuals. In patients whose renal function may depend on the activity of the renin-angiotensin-aldosterone system, such as patients with bilateral renal artery stenosis, unilateral renal artery stenosis to a solitary kidney, or severe congestive heart failure, treatment with agents that inhibit this system has been associated with oliguria, progressive azotemia, and rarely, acute renal failure and/or death. In susceptible patients, concomitant diuretic use may further increase risk.
Use of irbesartan should include appropriate assessment of renal function.
In hypertensive type 2 diabetic patients with proteinuria (≥900 mg/day), a population which has a high risk of renal artery stenosis, no patient treated with irbesartan in IDNT had an early acute rise in serum creatinine attributable to renal artery disease. (See ACTION AND CLINICAL PHARMACOLOGY; Clinical Trials; Hypertension and Type 2 Diabetic Renal Disease.)
Valvular Stenosis
There is concern on theoretical grounds that patients with aortic stenosis might be at particular risk of decreased coronary perfusion when treated with vasodilators because they do not develop as much afterload reduction.
Use in Children
Safety and effectiveness have not been established.
Use in the Elderly
Of the 4140 hypertensive patients receiving irbesartan in clinical studies, 793 patients were 65 years of age and over. No overall age-related differences were seen in the adverse effect profile but greater sensitivity in some older individuals cannot be ruled out.
General
The effect of irbesartan on the ability to drive and the use of machinery has not been studied, but based on its pharmacodynamic properties, irbesartan is unlikely to affect this ability. When driving vehicles or operating machinery, it should be taken into account that occasionally dizziness or weariness may occur during treatment of hypertension.
Drug Interactions
Diuretics
Patients on diuretics, and especially those in whom diuretic therapy was recently instituted, may occasionally experience an excessive reduction of blood pressure after initiation of therapy with irbesartan. The possibility of symptomatic hypotension with the use of irbesartan can be minimized by discontinuing the diuretic prior to initiation of treatment and/or lowering the initial dose of irbesartan (see WARNINGS - Hypotension, and DOSAGE AND ADMINISTRATION). No drug interaction of clinical significance has been identified with thiazide diuretics.
Agents increasing Serum Potassium
Since irbesartan decreases the production of aldosterone, potassium-sparing diuretics or potassium supplements should be given only for documented hypokalemia and with frequent monitoring of serum potassium. Potassium-containing salt substitutes should also be used with caution.
NSAIDs
In patients who are elderly, volume-depleted (including those on diuretic therapy), or with compromised renal function, coadministration of NSAIDs, including selective COX-2 inhibitors, with angiotensin II receptor antagonists, including irbesartan, may result in deterioration of renal function, including possible acute renal failure. These effects are usually reversible. Monitor renal function periodically in patients receiving irbesartan and NSAID therapy. The antihypertensive effect of angiotensin II receptor antagonists, including irbesartan, may be attenuated by NSAIDs including selective COX-2 inhibitors.
Lithium Salts
As with other drugs which eliminate sodium, lithium clearance may be reduced. Therefore, serum lithium levels should be monitored carefully if lithium salts are to be administered.
Warfarin
When irbesartan was administered as 300 mg once daily under steady-state conditions, no pharmacodynamic effect on PT (prothrombin time) was demonstrated in subjects stabilized on warfarin.
Digoxin
When irbesartan was administered as 150 mg once daily under steady-state conditions, no effect was seen on the pharmacokinetics of digoxin at steady-state.
Simvastatin
When irbesartan was administered in a small single-dose study with 12 young, healthy males aged 19 to 39, the single-dose pharmacokinetics of simvastatin were not affected by the concomitant administration of 300 mg irbesartan. Simvastatin values were highly variable whether simvastatin was administered alone or in combination with irbesartan.
ADVERSE REACTIONS
Irbesartan has been evaluated for safety in more than 4100 patients with essential hypertension including approximately 1300 patients for over 6 months and 400 patients for 1 year or more.
In placebo-controlled clinical trials, therapy was discontinued due to a clinical adverse event in 3.3 % of patients treated with irbesartan, versus 4.5 % of patients given placebo.
The following potentially serious adverse reactions have been reported rarely with irbesartan in controlled clinical trials: syncope, hypotension.
Adverse events occurring in ≥1% of the 2606 hypertensive patients in placebo-controlled clinical trials include the following:
| Body System/Reaction | Irbesartan n = 1965 Incidence (%) | Placebo n = 641 Incidence (%) |
General Abdominal Pain Chest pain Edema Fatigue | 1.4 1.8 1.5 4.3 | 2.0 1.7 2.3 3.7 |
Cardiovascular Tachycardia | 1.2 | 0.9 |
Dermatologic Rash | 1.3 | 2 |
Gastrointestinal Diarrhea Dyspepsia/Heartburn Nausea/Vomiting | 3.1 1.7 2.1 | 2.2 1.1 2.8 |
Musculoskeletal / Connective Tissue Musculoskeletal pain | 6.6 | 6.6 |
Nervous System Anxiety/Nervousness Headache Dizziness | 1.1 12.3 4.9 | 0.9 16.7 5.0 |
Respiratory Cough | 2.8 | 2.7 |
Urogenital System Urinary Tract Infection | 1.1 | 1.4 |
The incidence of hypotension or orthostatic hypotension occurred in 0.4% of irbesartan treated patients, unrelated to dosage, and in 0.2% of patients receiving placebo.
In addition, the following potentially important events occurred in < 1% of patients receiving irbesartan, regardless of drug relationship:
Body as a Whole: fever;
Cardiovascular: flushing, hypertension, myocardial infarction, angina pectoris, arrhythmic/ conduction disorder, cardio-respiratory arrest, heart failure, hypertensive crisis;
Dermatologic: pruritus, dermatitis, ecchymosis, erythema, urticaria, photosensitivity;
Endocrine: sexual dysfunction, libido change, gout;
Gastrointestinal: constipation, gastroenteritis, flatulence, distention abdomen, hepatitis;
Musculoskeletal: muscle cramp, arthritis, myalgia, muscle weakness;
Nervous System: sleep disturbance, numbness, somnolence, vertigo, depression, paresthesia, tremor, transient ischemic attack, cerebrovascular accident.
Renal/Genitourinary: abnormal urination;
Respiratory: epistaxis, tracheobronchitis, pulmonary congestion, dyspnea, wheezing;
Special Senses: visual disturbance, hearing abnormality, conjunctivitis, taste disturbance.
Postmarketing Experience
Angioedema (involving swelling of the face, lips, and/or tongue) has been reported rarely in postmarketing use. The following adverse reactions, regardless of drug relationship, have been reported in post-marketing use, syncope, asthenia, myalgia, jaundice, elevated liver function tests and impaired renal function including cases of renal failure in patients at risk (see PRECAUTIONS - Renal Impairment).
Cases of muscle pain, muscle weakness, myositis and rhabdomyolysis have been reported in patients receiving angiotensin II receptor blockers.
Clinical Studies in Hypertension and Type 2 Diabetic Renal Disease
In clinical studies in patients with hypertension and type 2 diabetic renal disease (see ACTION AND CLINICAL PHARMACOLOGY; Clinical Trials: Hypertension and Type 2 Diabetic Renal Disease), the adverse drug experiences were similar to those in clinical trials of hypertensive patients with the exception of orthostatic symptoms (dizziness, orthostatic dizziness, and orthostatic hypotension) observed in IDNT (The Irbesartan Diabetic Nephropathy Trial) (proteinuria ≥900mg/day, and serum creatinine from 1.0-3.0 mg/dL). In IDNT orthostatic symptoms occurred more frequently in the irbesartan group (dizziness 10.2%, orthostatic dizziness 5.4%, orthostatic hypotension 5.4%) than in the placebo group (dizziness 6.0%, orthostatic dizziness 2.7%, orthostatic hypotension 3.2%). The rates (percents) of discontinuations due to orthostatic symptoms for irbesartan versus placebo were: dizziness 0.3 vs 0.5; orthostatic dizziness 0.2 vs 0.0; and orthostatic hypotension, 0.0 vs 0.0.
Laboratory Test Findings
In controlled clinical trials of hypertension, clinically important differences in laboratory tests were rarely associated with irbesartan.
Liver Function Tests: In placebo-controlled trials, elevations of AST and ALT ≥3X upper limit of normal occurred in 0.1% and 0.2%, respectively, of irbesartan treated patients compared to 0.3% and 0.3%, respectively, of patients receiving placebo. The cumulative incidence of AST and/or ALT elevations ≥ 3X upper limit of normal was 0.4% in patients treated with irbesartan for a mean duration of over 1 year.
Hyperkalemia: For hypertension with type 2 diabetes and renal disease in clinical trials conducted in patients with diabetic renal disease, the laboratory test parameter profile was similar to that of hypertension, with the exception of hyperkalemia. In a placebo-controlled trial in 590 patients with hypertension, type 2 diabetes, microalbuminuria, and normal renal function (IRMA 2), hyperkalemia ≥5.5 mEq/L occurred in 29.4% of the patients in the irbesartan 300 mg group and 22% of the patients in the placebo group. Discontinuation for hyperkalemia occurred in 0.5% of the patients in the irbesartan group.
In another placebo-controlled trial in 1715 patients with hypertension, type 2 diabetes, proteinuria ≥ 900 mg/day, and serum creatinine ranging from 1.0 - 3.0 mg/dl (IDNT), hyperkalemia ≥ 5.5 mEq/L occurred in 46.3% of the patients in the irbesartan group and 26.3% of the patients in the placebo group. Discontinuation for hyperkalemia occurred in 2.1% and 0.4% of the patients in the irbesartan and placebo groups, respectively.
Creatinine, Blood Urea Nitrogen: Minor increases in blood urea nitrogen (BUN) or serum creatinine were observed in less than 0.7% of patients with essential hypertension treated with irbesartan alone versus 0.9% on placebo.
Hemoglobin: Mean decreases in hemoglobin of 0.16 g/dL were observed in patients receiving irbesartan. No patients were discontinued due to anemia.
Neutropenia: Neutropenia (<1000 cells/mm3) was observed in 0.3% of irbesartan treated patients compared to 0.5% of patients receiving placebo.
In clinical trials, the following were noted to occur with an incidence of <1%, regardless of drug relationship: anemia, thrombocytopenia, lymphocytopenia, and increased CPK.
SYMPTOMS AND TREATMENT OF OVERDOSAGE
Few cases of overdosage with irbesartan have been reported, with no significant clinical sequelae. Reported overdoses ranged from 600 - 900 mg daily. Durations of overdosing ranged from 2 - 3 weeks up to 30 days and over. No complaints were associated with the overdoses and no clinical sequelae were observed. Experience in adults exposed to doses of up to 900 mg/day for 8 weeks revealed no toxicity.
The most likely manifestations of overdosage are expected to be hypotension and tachycardia; bradycardia might also occur from overdose.
No specific information is available on the treatment of overdosage with irbesartan. The patient should be closely monitored, and the treatment should be symptomatic and supportive.
Suggested measures include induction of emesis and/or gastric lavage. Activated charcoal may be useful in the treatment of overdosage.
Irbesartan is not removed by hemodialysis.
DOSAGE AND ADMINISTRATION
Initiation of therapy requires consideration of recent antihypertensive drug treatment, the extent of blood pressure elevation, salt restriction, and other pertinent clinical factors. The dosage of other antihypertensive agents used with IRBESARTAN (irbesartan) may need to be adjusted.
IRBESARTAN may be administered with or without food.
Essential Hypertension
The recommended initial dose of IRBESARTAN is 150 mg once daily. In patients whose blood pressure is not adequately controlled, the daily dose may be increased to 300 mg.
Essential Hypertension with Type 2 Diabetic Renal Disease
The recommended initial dose of IRBESARTAN is 150 mg once daily. In patients whose blood pressure is not adequately controlled, the daily dose may be increased to 300 mg once daily, the preferred maintenance dose.
No initial dosage adjustment is required in the elderly, or in patients with renal impairment (see ACTION AND CLINICAL PHARMACOLOGY- Pharmacokinetics and PRECAUTIONS – Use in the Elderly). However, due to the apparent greater sensitivity of hemodialysis patients, an initial dose of 75 mg is recommended in this group of patients.
No initial dosage adjustment is required in patients with mild-to-moderate hepatic impairment (see ACTION AND CLINICAL PHARMACOLOGY - Pharmacokinetics).
Concomitant Diuretic Therapy
In patients receiving diuretics, IRBESARTAN therapy should be initiated with caution, since these patients may be volume-depleted and thus more likely to experience hypotension following initiation of additional antihypertensive therapy. Whenever possible, all diuretics should be discontinued two to three days prior to the administration of IRBESARTAN to reduce the likelihood of hypotension (see WARNINGS - Hypotension, and PRECAUTIONS - Drug Interactions). If this is not possible because of the patient’s condition, IRBESARTAN should be administered with caution and the blood pressure monitored closely. The recommended starting dose of IRBESARTAN is 75 mg once daily in hypovolemic patients (see WARNING - Hypotension). Thereafter, the dosage should be adjusted according to the individual response of the patient.
PHARMACEUTICAL INFORMATION
I. DRUG SUBSTANCE
Trade Name: PrRAN™-IRBESARTAN
Proper Name: Irbesartan USP
Chemical Name: 2-butyl-3-[(21-(1H-tetrazol-5-yl)biphenyl-4-yl)methyl]-1,3-diazaspiro [4,4] non-1-en-4-one.
Empirical Formula: C25 H28 N6O
Structural Formula:
N
N
O
CH 3
N
N
N
H N
Irbesartan
Molecular Weight: 428.53
Description: Irbesartan USP is a white to off-white crystalline powder. It is a nonpolar compound with a partition coefficient (octanol/water) of 10.1 at a pH of 7.4. Irbesartan is slightly soluble in alcohol and methylene chloride and practically insoluble in water.
II. COMPOSITION
In addition to the active ingredient, irbesartan USP, each tablet contains calcium stearate, lactose monohydrate, microcrystalline cellulose, pregelatinized starch, poloxamer 188 and sodium starch glycolate.
III. STORAGE
IRBESARTAN (Irbesartan Tablets USP) can be stored at room temperature (15° C - 30° C).
AVAILABILITY OF DOSAGE FORMS
IRBESARTAN (irbesartan) 75 mg tablets are white to off-white, oval shaped, biconvex uncoated tablets, debossed with ‘RI 21’ on one side and plain on other.
IRBESARTAN (irbesartan) 150 mg tablets are white to off-white, oval shaped, biconvex uncoated tablets debossed with ‘RI 22’ on one side and plain on other.
IRBESARTAN (irbesartan) 300 mg tablets are white to off-white, oval shaped, biconvex uncoated tablets debossed with ‘RI 23’ on one side and plain on other.
IRBESARTAN (irbesartan) 75, 150 and 300 mg tablets are available in bottles of 30, 100 and 500 tablets.
TOXICOLOGY
Acute Toxicity
| Species | Sex (N) | Route | LD50 (mg/kg) |
| Mouse | M (5) F (5) | PO | > 2000 |
| Rat | M (5) F (5) | PO | > 2000 |
| Mouse | M (5) F (5) | IV | > 50 |
| Rat | M (5) F (5) | IV | > 50 |
| Mouse | M (5) F (5) | IP | 200 - 2000 |
| Rat | M (5) F (5) | IP | 200 - 2000 |
After single administration, toxicity was slight and no target organ was identified. Very few toxic effects, characterized by pilo-erection and/or somnolence were noted at 2000 mg/kg by the oral route, 200 mg/kg by the intraperitoneal route and 50 mg/kg by the intravenous route. Acute oral toxicity studies with irbesartan in mice and rats indicated acute lethal doses were in excess of 2000mg/kg, about 25 - 50 fold the maximum human dose (300 mg) on a mg/m2 basis, respectively.
Subacute and Chronic Toxicity
| Species/ Strain | Sex (N/Dose) | Dose (mg/kg/day) | Route | Time | Effects | ||||
| SUBACUTE TOXICITY | |||||||||
| Rat | M (10) F (10) | 0, 30 , 70 , 150 | po | 4 weeks |
| ||||
| Rat | M (10) F (10) | 0, 0.8 , 2 , 5 | iv | 16 days |
| ||||
| Monkey | M (3) F (3) | 0 , 10, 30 , 90 | po | 4 weeks |
| ||||
| Monkey | M (3) F (3) | 0 , 250 , 500 , 1000 | po | 4 weeks |
| ||||
| Monkey | M (3) F (3) | 0 , 0.8 , 2 , 5 | iv | 2 weeks |
| ||||
| Rat | M (20) - F (20) [main study] M (10) - F (10) [reversibility study for control and high dose groups] M (5) - F (5) [toxicokinetics study] | 0 , 10 , 30 , 90 | po | 26 weeks |
| ||||
| CHRONIC TOXICITY | |||||||||
| Rat | M (20) - F (20) [main study] M (10) - F (10) | 0 , 0 , 250 , 500, 1000 | po | 26 weeks |
| ||||
| Species/ Strain | Sex (N/Dose) | Dose (mg/kg/day) | Route | Time | Effects |
[reversibility study for control and high dose groups] M (5) - F (5) [toxicokinetics study] | activity of irbesartan and reversible.
| ||||
| Monkey | M (5) - F (5) [main study] M (3) - F (3) [reversibility study for control and high dose groups)] | 0, 10, 30, 90 | po | 6 months |
|
| Monkey | M (5) F (5) | 0, 20, 100, 500 | po | 52 weeks | Irbesartan was well tolerated and most of the changes observed were considered to be due to the pharmacological activity of the drug:
|
Subacute and Chronic Toxicity (Cont’d)
After repeated oral administrations at dose levels up to 1000 mg/kg per day, most of the treatment-related effects noted in all species are linked to the pharmacological activity of irbesartan. The kidney can be considered as the primary target organ: hyperplasia/hypertrophy of the juxtaglomerular apparatus which was observed in all species, is a direct consequence of the interaction with the renin-angiotensin system. Irbesartan also induced some hematology (slight decrease in erythrocyte parameters) and blood biochemistry variations (slight increased in urea, creatinine, phosphorus, potassium and calcium levels) likely due to a disturbance in the renal blood flow, and a slight decrease in heart weight which could result from a decrease in cardiac work load due to decreased peripheral vascular resistance. At high doses (> 500 mg/kg per day), degenerative changes of the kidney were noted which could be secondary to prolonged hypotensive effects.
Reproduction and Teratology
Fertility and reproductive performance were not affected in studies of male and female rats even at oral doses of irbesartan causing pronounced toxicity (up to 650 mg/kg/day). No significant effects on the number of corpora lutea, implants, or live fetuses were observed. Irbesartan did not affect survival, development, or reproduction of offspring except for a slight decrease of body weight gain during lactation which was reversible after weaning.
In a study of rats receiving maternally toxic doses of irbesartan (650 mg/kg/day), transient effects were observed in fetuses. These effects included increased incidences of renal pelvic cavitation at doses ≥50 mg/kg/day and subcutaneous edema at doses ≥180 mg/kg/day. Slight decreases in body weight gain were noted (prior to weaning) in offspring of females receiving irbesartan at doses ≥ 50 mg/kg/day. In rabbits, maternally toxic doses of irbesartan (30 mg/kg/day) were associated with maternal mortality and abortion. Surviving females receiving this dose had a slight increase in early resorption. However, no teratogenic effect was observed. Radioactivity was present in the rat and rabbit fetus during late gestation and in rat milk following oral doses of radiolabeled irbesartan. These findings are attributed to drug exposure in late gestation and during lactation.
Carcinogenicity and Mutagenicity
No evidence of carcinogenicity was observed when irbesartan was administered at doses of up to 500/1000 mg/kg/day (males/females, respectively) in rats and 1000 mg/kg/day in mice for 2 years. These doses provided systemic exposures of 3.6 - 24.9 times (rats) and 3.8 - 6.2 times (mice) the exposures in humans receiving 300 mg daily.
Irbesartan was not mutagenic in a battery of in vitro tests (Ames microbial test, rat hepatocyte DNA repair test, V79 mammalian cell forward gene mutation assay). Irbesartan was negative in several tests for induction of chromosomal aberrations (in vitro - human lymphocyte assay; in vivo - mouse micronucleus study).
SELECTED BIBLIOGRAPHY
- 1.
Cazaubon C, Gougat J, Bousquet F, Guiraudou P, Gayraud R, Lacour C, et al.
Pharmacological characterization of SR 47436, a new nonpeptide AT1 subtype angiotensin II receptor antagonist. J Pharmacol Exp Ther 1993; 265:826-834
- 2.
Hagmann M, Burnier M, Nussberger J, Leenhardt AF, Brouard R, Waeber B, et al.
Natriuretic and hormonal effects of SR 47436 (BMS 186295), a new angiotensin II receptor antagonist in normotensive volunteers. Am J Hyperten 1994; 7 (4,Pt.2):13A
- 3.
Marino MR, Langenbacher KM, Raymond RH, Whigan D, and Ford NF
Pharmacokinetics (pK) and antihypertensive effects of irbesartan (an AII receptor antagonist) in subjects with hypertension. J Hyperten 1996; 14(1):S348
- 4.
Martinez F, Schmitt F, Savoiu C, Leenhardt AF, Brouard R, Peronnet P, et al. Effect of
SR 47436 (BMS 186295) on renal hemodynamics and on glomerular permselectivity in healthy humans. J Am Soc Nephrol 1994; 5: 607
- 5. McIntyre M, McFadyen RJ, Meredith PA, Bruard R, and Reid JL Dose-ranging study of the angiotensin II receptor antagonist irbesartan (SR 47436 / BMS 186295) on blood pressure and neurohormonal effects in salt-deplete men. J Cardiovas Pharmacol 1996; 28:101-106
- 6. Ribstein J, Sissmann J, Picard A, Bouroudian M, and Mimran A. Effects of the angiotensin II antagonist SR 47436 (BMS 186295) on the pressor response to exogenous angiotensin II and the renin-angiotensin system in sodium replete normal subjects. J Hypertens 1994; 12:131
- 7.
Sissmann J, Bouroudian M, Armagnac C, Donazollo Y, Latreille M, and Panis R.
Angiotensin II blockade in healthy volunteers: Tolerability and impact on renin angiotensin system components of single and repeated doses of a new angiotensin II receptor antagonist SR 47436 (BMS 186295). J Hypertens 1994; 12:S92
- 8.
Binding of Irbesartan with Human Serum Proteins: a Re-evaluation (Horace Davi, Sept.
1998).
- 9. The Diabetes and Complications DCCT Research Group. Effect of intensive therapy on the development and progression of diabetic nephropathy in the diabetes control and complications trials. Kidney Int. 1995;47:1703-1720.
- 10. Ravid M, Lang R, Rachman R, Lishner M. Lont-term renoprotective effect of angiotensin-converting enzyme inhibition in non-insulin-dependent diabetes mellitus. Arch Intern Med. 196; 156:286-289.
- 11. Maki DD, Ma JZ, Louis TA, Kasiske BL. Long term effects of antihypertensive agents on proteinuria and renal function. Arch Intern Med. 1995;155:1073-1080.
- 12. Cazaubon C, Gougat J, Bousquet F, et al. Pharmacological characterization of SR 47436 a new nonpeptide AT1 subtype angiotensin II receptor antagonist. J Pharmacol Exp Ther. 1993;265:826-834.
- 13. Necciari J, Denolle T, Le Coz F, Donazollo Y, Pastor G, Sissmann J. Pharmacokinetics of SR 47436 BMS-186295, a new angiotensin II antagonist in man. J Hypertens. 1994;12: 88.
- 14. Van Den Meiracker AH, Admiraal PJ, Janssen JA, et al. Hemodynamic and biochemical effects of the ATI receptor antagonist irbesartan in hypertension. Hypertension. 1995;25:22-29.
- 15.
Parving HH et al. The Effects of Irbesartan on The Development of Diabetic
Nephropathy in Patients with Type 2 Diabetes Mellitus (IRMA 2) N Engl J Med 2001; 345(12):870-878
- 16. Lewis EJ et al. Renoprotective Effect of the Angiotensin-Receptor Antagonist Irbesartan in Patients with Nephropathy Due to Type 2 Diabetes. The Irbesartan Diabetic Nephropathy Trial (IDNT). N Engl J Med 2001; 345 (12):851-860
- 17.
Ribstein J, Picard a, Armagnac C, Sissmann J and Mimran A. Inhibition of the Acute
Effects of Angiotensin Ii by the Receptor Antagonist Irbesartan in Normotensive Men. J Cardiovas Pharmacol 2001; 37:449-460
- 18. Product monograph of AVAPRO® (irbesartan) Tablets, 75, 150 and 300 mg, Sanofi-aventis Canada Inc., Date of Revision: 27 August 2012, Submission Control No. 155242.