


Product Monograph - Jamp Colesevelam
INDICATIONS AND CLINICAL USE
JAMP Colesevelam (colesevelam) is indicated for the reduction of cholesterol blood level in patients with hypercholesterolemia (Fredrickson Type IIa) as an adjunct to diet and lifestyle changes, when the response to these measures has been inadequate, in patients:
- who are not adequately controlled with an HMG-CoA reductase inhibitor (statin) alone, or
- who are unable to tolerate a statin.
Limitations of Use
Colesevelam has not been studied in Fredrickson Type I, IIb, III, IV and V dyslipidemias.
Geriatrics (≥65 years of age)
There is no need for dose adjustment when JAMP Colesevelam is administered to elderly patients.
Pediatrics (<18 years of age)
The safety and efficacy of colesevelam have not been established in children and adolescent patients; therefore, the use of JAMP Colesevelam in these patient populations is not recommended.
CONTRAINDICATIONS
- Patients who are hypersensitive to this drug or to any ingredient in the formulation or component of the container. For a complete listing, see the Dosage Forms, Composition and Packaging section of the product monograph.
- Bowel or biliary obstruction
WARNINGS AND PRECAUTIONS
General
Prior to initiating therapy with JAMP Colesevelam (colesevelam), if secondary causes of hypercholesterolemia (i.e., poorly controlled diabetes mellitus, hypothyroidism, nephrotic syndrome, dysproteinemias, obstructive liver disease) are considered, these should be diagnosed and properly treated.
For patients on cyclosporine starting or stopping JAMP Colesevelam or patients on JAMP Colesevelam with a need to start cyclosporine: Colesevelam reduces the bioavailability of cyclosporine (see DRUG INTERACTIONS). Patients starting on cyclosporine already taking JAMP Colesevelam should have their cyclosporine blood concentrations monitored as normal and their dose adjusted as normal. Patients starting on JAMP Colesevelam already taking cyclosporine should have their blood concentrations monitored prior to combination therapy and frequently monitored immediately starting co-therapy with the cyclosporine dose adjusted accordingly. It should be noted that stopping JAMP Colesevelam therapy will result in increased cyclosporine blood concentrations. Therefore, patients taking both cyclosporine and JAMP Colesevelam should have their blood concentrations monitored prior to and frequently after when JAMP Colesevelam therapy is stopped with their cyclosporine dose adjusted accordingly.
Endocrine and Metabolism:
When treating hypercholesterolemic patients with type 2 diabetes mellitus who initiate or are currently on antidiabetic pharmacologic treatment regimen, the fasting plasma glucose (FPG) lowering effect of colesevelam as well as subsequent HbA1c monitoring should be considered, since this effect has been observed with colesevelam when administered with some antidiabetic agents
Gastrointestinal
The safety and efficacy of colesevelam in patients with dysphagia, swallowing disorders, severe gastrointestinal motility disorders, inflammatory bowel disease, liver failure or major gastrointestinal tract surgery have not been established. Consequently, caution should be exercised when JAMP Colesevelam is used in patients with these disorders.
JAMP Colesevelam can induce or worsen present constipation. The risk of constipation should especially be considered in patients with coronary heart disease and angina pectoris.
Hematologic
Anticoagulant therapy should be monitored closely in patients receiving warfarin or similar agents, since bile acid sequestrants, like colesevelam, have been shown to reduce absorption of vitamin K and therefore interfere with warfarin’s anticoagulant effect (see DRUG INTERACTIONS).
Hepatic/Biliary/Pancreatic
Caution should be exercised when treating patients with triglyceride levels greater than 3.4 mmol/L due to the triglyceride increasing effect with colesevelam. Safety and efficacy are not established for patients with triglyceride levels greater than 3.4 mmol/L, since such patients were excluded from the clinical studies.
Sexual Function/Reproduction
JAMP Colesevelam can affect the bioavailability of the oral contraceptive pill when administered simultaneously. It is important to ensure that JAMP Colesevelam is administered at least 4 hours after the oral contraceptive pill to minimize the risk of any interaction (see DRUG INTERACTIONS).
Special Populations
Pregnant Women
No clinical data are available on the use of colesevelam in pregnant women. Animal studies do not indicate direct or indirect harmful effects with respect to pregnancy, embryonic/fetal development, parturition or post-natal development (see TOXICOLOGY). Caution should be exercised when prescribing to pregnant women.
Nursing Women
The safety of colesevelam has not been established in breast-feeding women. Caution should be exercised when prescribing to breast-feeding women.
Pediatrics (<18 years of age)
The safety and efficacy of colesevelam have not been established in children and adolescent patients; therefore, the use of JAMP Colesevelam in these patient populations is not recommended.
Geriatrics (≥65 years of age)
Of the 1350 patients enrolled in the hyperlipidemia clinical studies, 349 (26%) were ≥65 years old, and 58 (4%) were ≥75 years old. No overall differences in safety or effectiveness were observed between these subjects and younger subjects, and other reported clinical experience has not identified differences in responses between the elderly and younger patients, but greater sensitivity of some older individuals cannot be ruled out.
Monitoring and Laboratory Tests
Serum total-C, LDL-C and triglyceride levels should be determined periodically during treatment to confirm favourable initial and adequate long-term responses.
The impact on glycemic levels of colesevelam when used concomitantly with antidiabetic pharmacologic treatment regimens should be monitored by periodic measurements of blood glucose and HbA1c levels. When JAMP Colesevelam is co-administered with metformin extended-release formulation, the physician should monitor glucose more closely.
ADVERSE REACTIONS
Adverse Drug Reaction Overview
In monotherapy clinical trials, the most common (incidence ≥2% and greater than placebo) adverse reactions with colesevelam included constipation, dyspepsia, and nausea.
Post-marketing ADR reports include bowel obstruction, dysphagia, esophageal obstruction, fecal impaction, hypertriglyceridemia, pancreatitis and increased transaminases. Additionally, some interaction reports were received describing changes in phenytoin levels, reduced International Normalized Ratio (INR), and elevated thyroid-stimulating hormone (TSH) (see DRUG INTERACTIONS).
Clinical Trial Adverse Drug Reactions
Because clinical trials are conducted under very specific conditions the adverse reaction rates observed in the clinical trials may not reflect the rates observed in practice and should not be compared to the rates in the clinical trials of another drug. Adverse drug reaction information from clinical trials is useful for identifying drug-related adverse events and for approximating rates.
In the lipid-lowering trials, 807 patients received at least one dose of colesevelam (total exposure 199 patient-years). In clinical trials for the reduction of LDL-C, 68% of patients receiving colesevelam vs. 64% of patients receiving placebo reported an adverse reaction.
In 7 double-blind, placebo-controlled, clinical trials, 807 patients with primary hyperlipidemia (age range 18-86 years, 50% women, 90% Caucasians, 7% Blacks, 2% Hispanics, 1% Asians) and elevated LDL- C were treated with colesevelam 1.5 g/day to 4.5 g/day from 4 to 24 weeks.
Table 1 summarizes the placebo-controlled monotherapy clinical studies of colesevelam for hyperlipidemia: Adverse reactions reported in ≥1% of patients and numerically more commonly than in patients given placebo, regardless of investigator assessment of causality.
Table 1 - Placebo-Controlled Monotherapy Clinical Studies of Colesevelam for Hyperlipidemia: Adverse Reactions Reported in ≥1% of Patients and Numerically More Commonly than in Patients Given Placebo, Regardless of Investigator Assessment of Causality
| BODY SYSTEM | PLACEBO (n=258) N % | Colesevelam ONLY (n=807) N % | ||||||||
| Body as a whole | ||||||||||
| Flu syndrome | 8 | 3.1 | 26 | 3.2 | ||||||
| Asthenia | 5 | 1.9 | 29 | 3.6 | ||||||
| Accidental injury | 7 | 2.7 | 30 | 3.7 | ||||||
| Chest pain | 2 | 0.8 | 11 | 1.4 | ||||||
| Allergic reaction | 2 | 0.8 | 9 | 1.1 | ||||||
| Digestive system | ||||||||||
| Constipation | 18 | 7.0 | 89 | 11.0 | ||||||
| Dyspepsia | 9 | 3.5 | 67 | 8.3 | ||||||
| Nausea | 10 | 3.9 | 34 | 4.2 | ||||||
| Gastroenteritis | 1 | 0.4 | 9 | 1.1 | ||||||
| Respiratory system | ||||||||||
| Pharyngitis | 5 | 1.9 | 26 | 3.2 | ||||||
| Rhinitis | 8 | 3.1 | 26 | 3.2 | ||||||
| Nervous system | ||||||||||
| Dizziness | 3 | 1.2 | 13 | 1.6 | ||||||
| Anxiety | 1 | 0.4 | 10 | 1.2 | ||||||
| Musculoskeletal system | ||||||||||
| Myalgia | 1 | 0.4 | 17 | 2.1 | ||||||
| Arthritis | 2 | 0.8 | 10 | 1.2 | ||||||
| Skin and appendages | ||||||||||
| Rash | 3 | 1.2 | 14 | 1.7 | ||||||
| Contact dermatitis | 2 | 0.8 | 10 | 1.2 | ||||||
Colesevelam treatment is well-tolerated, though gastrointestinal symptoms (usually mild) are common. In general, the percentages of patients reporting common adverse events were similar in the placebo and colesevelam-only treatment categories. Only constipation and dyspepsia were reported by a higher percentage of colesevelam-only patients.
Combination with a HMG-CoA Reductase Inhibitor
Colesevelam has been evaluated for safety in combination studies with a statin in 279 patients. In general, adverse experiences were similar between colesevelam administered with a statin and a statin alone. However, the frequency of constipation was higher (9.3% vs 5.3%) in patients receiving colesevelam administered with a statin than in patients treated with a statin alone, as was the frequency of dyspepsia (5.4% vs 3.8%). No other adverse events were reported in ≥2% of patients and at an incidence significantly greater on the combination than on the statin alone.
Nausea occurred less frequently in patients receiving colesevelam administered with a statin (3.2%) than in patients treated with a statin alone (4.3%).
Table 2 - Placebo-Controlled Combination Clinical Studies of Colesevelam for Hyperlipidemia: Adverse Reactions Reported in ≥1% of Patients Regardless of Investigator Assessment of Causality.
| BODY SYSTEM | STATIN + PLACEBO (n=209) N % | STATIN + COLESEVELAM (n=279) N % | ||
| Body as a whole | ||||
| Headache | 13 | 6.2 | 16 | 5.7 |
| Flu syndrome | 6 | 2.9 | 4 | 1.4 |
| Digestive system | ||||
| Constipation | 11 | 5.3 | 26 | 9.3 |
| Flatulence | 18 | 8.6 | 18 | 6.5 |
| Dyspepsia | 8 | 3.8 | 15 | 5.4 |
| Diarrhea NOS | 15 | 7.2 | 9 | 3.2 |
| Nausea | 9 | 4.3 | 9 | 3.2 |
| Abdominal tenderness | 4 | 1.9 | 6 | 2.2 |
| Dry mouth | 0 | 0.0 | 3 | 1.1 |
| Abnormal stools | 1 | 0.5 | 3 | 1.1 |
| Musculoskeletal system | ||||
| Myalgia | 9 | 4.3 | 11 | 3.9 |
| Skin and appendages | ||||
| Dry skin | 0 | 0.0 | 3 | 1.1 |
| Urogenital system | ||||
| Urinary tract infection NOS | 0 | 0.0 | 4 | 1.4 |
Less Common Clinical Trial Adverse Drug Reactions (<1%)
Less common clinical trial treatment-emergent adverse events (<1% and greater than placebo) possibly or probably related to colesevelam:
Digestive System: Anorexia, eructation, dysphagia, increased appetite, liver function tests abnormal, colitis, glossitis, stomatitis.
Body as a Whole: Asthenia, chest pain, pain, LE syndrome. Nervous System: Hyperkinesia, anxiety, nervousness, paresthesia. Musculoskeletal System: Myalgia, leg cramps.
Respiratory System: Pharyngitis, dyspnea, rhinitis, sputum increased.
Skin and Appendages: Nail disorder.
Special Senses: Taste perversion, conjunctivitis.
Metabolic and Nutritional Disorders: SGPT increased, peripheral edema, SGOT increased.
Urogenital System: Urinary urgency.
Cardiovascular System: Hypertension.
Post-Market Adverse Drug Reactions
The following additional adverse reactions have been identified during post-market use of colesevelam. Because these reactions are reported voluntarily from a population of uncertain size, it is generally not possible to reliably estimate their frequency or establish a causal relationship to drug exposure.
Drug Interactions with concomitant colesevelam administration include:
- Increased seizure activity or decreased phenytoin levels in patients receiving phenytoin. Phenytoin should be administered 4 hours prior to JAMP Colesevelam.
Reduced International Normalized Ratio (INR) in patients receiving warfarin therapy.
In warfarin-treated patients, INR should be monitored frequently during JAMP Colesevelam initiation then periodically thereafter.
- Elevated thyroid-stimulating hormone (TSH) in patients receiving thyroid hormone replacement therapy. Thyroid hormone replacement should be administered 4 hours prior to JAMP Colesevelam [See DRUG INTERACTIONS].
Gastrointestinal Adverse Reactions
Bowel obstruction (in patients with a history of bowel obstruction or resection), dysphagia, or esophageal obstruction (occasionally requiring medical intervention), fecal impaction, pancreatitis, abdominal distension, exacerbation of hemorrhoids,
and increased transaminases.
Laboratory Abnormalities
Hypertriglyceridemia
Metabolism and Nutrition Disorders
Hypoglycaemia
DRUG INTERACTIONS
Overview
JAMP Colesevelam may affect the bioavailability of other medicinal products. Therefore, when a drug interaction cannot be excluded with a concomitant medicinal product, JAMP Colesevelam (colesevelam) should be administered at least four hours after the concomitant medication to minimize the risk of reduced absorption of the concomitant medication
When administering medicinal products for which alterations in blood levels could have a clinically significant effect on safety or efficacy, physicians should consider monitoring serum levels or effects.
Interaction studies have only been performed in adults.
In interaction studies in healthy volunteers, colesevelam had no effect on the bioavailability of digoxin, metoprolol, quinidine, valproic acid, and warfarin. Colesevelam decreased the Cmax and AUC of sustained-release verapamil by approximately 31% and 11%, respectively. Since there is a high degree of variability in the bioavailability of verapamil, the clinical significance of this finding is unclear.
In pharmacokinetic interaction studies in patients, colesevelam had no effect on the bioavailability of fenofibrate and lovastatin.
There have been very rare reports of reduced phenytoin levels in patients who have received colesevelam administered with phenytoin.
Drug-Drug Interactions
Table 3 lists the drugs that have been tested in in vitro or in vivo drug interaction studies with colesevelam and/or drugs with post-marketing reports consistent with potential drug-drug interactions. Orally administered drugs that have not been tested for interaction with colesevelam, especially those with a narrow therapeutic index, should also be administered at least 4 hours prior to JAMP Colesevelam. Alternatively, the physician should monitor drug levels of the co-administered drug.
Table 3: Drugs Tested in In Vivo Binding or In Vivo Drug Interaction Testing or Post-Marketing Reports
| Drugs with a known interaction with colesevelama | Glyburide, levothyroxine, and oral contraceptives containing ethinyl estradiol and norethindrone |
Drugs with post-marketing reports consistent with potential drug-drug interactions when co-administered with colesevelam | phenytoina, warfarinb |
| Drugs that do not interact with colesevelam based on in vitro or in vivo testing | digoxin, warfarinb, fenofibrate, lovastatin, metoprolol, pioglitazone, quinidine, repaglinide, valproic acid, verapamil |
a Should be administered at least 4 hours prior to JAMP Colesevelam
b No significant alteration of warfarin drug levels with warfarin and colesevelam coadministration in an in vivo study which did not evaluate warfarin pharmacodynamics (INR). (see Post-Marketing Adverse Drug Reactions)
Anticoagulant therapy
Anticoagulant therapy should be monitored closely in patients receiving warfarin or similar agents, since bile acid sequestrants have been shown to reduce absorption of vitamin K and therefore interfere with warfarin's anticoagulant effect. Specific clinical interaction studies with colesevelam and vitamin K have not been performed.
Levothyroxine
In an interaction study in healthy volunteers, colesevelam reduced the AUC and Cmax of levothyroxine when administered either concomitantly or after 1 hour. No interaction was observed when colesevelam was administered at least four hours after levothyroxine.
Oral contraceptive pill
In an interaction study in healthy volunteers, colesevelam reduced the Cmax of norethindrone as well as the AUC and Cmax of ethinylestradiol when administered simultaneously with the oral contraceptive pill. This interaction was also observed when colesevelam was administered one hour after the oral contraceptive pill. However, no interaction was observed when colesevelam was administered four hours after the oral contraceptive pill.
Cyclosporine
In an interaction study in healthy volunteers, co-administration of colesevelam and cyclosporine significantly reduced the AUC0-inf and Cmax of cyclosporine by 34% and 44%, respectively. Therefore, advice is given to closely monitor cyclosporine blood concentrations (see also section 4.4). In addition, based on theoretical grounds JAMP Colesevelam should be administered at least 4 hours after cyclosporine in order to further minimize the risks related to the concomitant administration of cyclosporine and JAMP Colesevelam. Furthermore, JAMP Colesevelam should always be administered at the same times consistently since the timing of intake of JAMP Colesevelam and cyclosporine could theoretically influence the degree of reduced bioavailability of cyclosporine.
Statins
When colesevelam was co-administered with statins in clinical studies, an expected add-on LDL-C lowering effect was observed, and no unexpected effects were observed. Interaction studies with colesevelam in combination with pravastatin, rosuvastatin, or high dose HMG-CoA reductase inhibitors have not been performed.
Antidiabetic agents
When colesevelam was co-administered with some antidiabetic agents in clinical studies (metformin, insulin, sulfonylureas) an add-on fasting plasma glucose lowering, effect was observed.
Co-administration of colesevelam and glyburide caused a decrease in the AUC0-inf and Cmax of glyburide by 32% and 47%, respectively. No interaction was observed when colesevelam was administered four hours after glyburide. Colesevelam increased levels of metformin when co-administered with metformin extended-release formulation.
Co-administration of colesevelam and repaglinide had no effect on the AUC and caused a 19% reduction in the Cmax of repaglinide, the clinical significance of which is unknown. No interaction was observed when colesevelam was administered one hour after repaglinide.
No interaction was observed when colesevelam and pioglitazone were administered simultaneously in healthy volunteers.
Other forms of interaction
Colesevelam did not induce any clinically significant reduction in the absorption of vitamins A, D, E or K during clinical studies of up to one year. However, caution should be exercised when treating patients with a susceptibility to vitamin K or fat-soluble vitamin deficiencies, such as patients with malabsorption. In these patients, monitoring vitamin A, D and E levels and assessing vitamin K status through the measurement of coagulation parameters is recommended and the vitamins should be supplemented if necessary.
Drug-Food Interactions
Interactions with food have not been established.
Drug-Herb Interactions
Interactions with herbal products have not been established.
Drug-Laboratory Interactions
Interactions with laboratory tests have not been established. Post marketing reports of hypertriglyceridemia (see Post-Market Adverse Drug Reactions).
Drug-Lifestyle Interactions
JAMP Colesevelam has no or negligible influence on the ability to drive and use machines.
DOSAGE AND ADMINISTRATION
Dosing Considerations
Prior to initiating therapy with JAMP Colesevelam (colesevelam), if secondary causes of hypercholesterolemia (i.e., poorly controlled diabetes mellitus, hypothyroidism, nephrotic syndrome, dysproteinemias, obstructive liver disease) are considered, these should be diagnosed and properly treated. (see WARNINGS AND PRECAUTIONS)
Recommended Dose and Dosage Adjustment
Combination therapy
The recommended dose of JAMP Colesevelam is 4 to 6 tablets per day. The maximum recommended dose is 3 tablets taken twice per day with meals or 6 tablets taken once per day with a meal.
Clinical trials have shown that colesevelam and atorvastatin, lovastatin or simvastatin can be co-administered or dosed apart.
Monotherapy
The recommended starting dose of JAMP Colesevelam is 3 tablets taken twice per day with meals or
6 tablets once per day with a meal. The maximum recommended dose is 7 tablets per day.
During therapy, the cholesterol-lowering diet should be continued, and serum total-C, LDL-C and triglyceride levels should be determined periodically during treatment to confirm favourable initial and adequate long-term responses.
When a drug interaction cannot be excluded with a concomitant medicinal product, JAMP Colesevelam should be administered at least four hours after the concomitant medication in order to minimize the risk of reduced absorption of the concomitant medication (see DRUG INTERACTIONS).
Missed Dose
If a dose is forgotten, it may be taken with a later meal. But never take in one day more than the total number of tablets prescribed in a single day. Double dosing is not advisable.
Administration
JAMP Colesevelam tablets should be taken orally with a meal and liquid.
OVERDOSAGE
Since colesevelam is not absorbed, the risk of systemic toxicity is low. Gastrointestinal symptoms could occur. Doses in excess of the maximum recommended dose (4.5 g per day (7 tablets)) have not been tested.
For the most recent information in the management of a suspected drug overdose, contact your regional poison control centre or Health Canada’s toll-free number, 1-844 POISON-X (1-844-764-7669).
Should overdosage occur, however, the chief potential harm would be obstruction of the gastrointestinal tract. The location of such potential obstruction, the degree of obstruction and the presence or absence of normal gut motility would determine treatment.
ACTION AND CLINICAL PHARMACOLOGY
Mechanism of Action
The mechanism of action for the activity of colesevelam, the active substance in JAMP Colesevelam, has been evaluated in several in vitro and in vivo studies. These studies have demonstrated that colesevelam binds bile acids, including glycocholic acid, the major bile acid in humans. Cholesterol is the sole precursor of bile acids. During normal digestion, bile acids are secreted into the intestine. A major portion of bile acids is then absorbed from the intestinal tract and returned to the liver via the enterohepatic circulation.
Bile acid sequestrants alter the bile acid pool composition, which might explain the impact on glycemic levels associated with these drugs, although the mechanism is unknown.
Pharmacodynamics
Colesevelam is a non-absorbed, lipid-lowering polymer that binds bile acids in the intestine, impeding their reabsorption. The LDL-C lowering mechanism of bile acid sequestrants has been previously established as follows: as the bile acid pool becomes depleted, the hepatic enzyme, cholesterol 7-α-hydroxylase, is upregulated, which increases the conversion of cholesterol to bile acids. This causes an increased demand for cholesterol in the liver cells, resulting in the dual effects of increasing transcription and activity of the cholesterol biosynthetic enzyme, hydroxymethyl-glutaryl-coenzyme A (HMG-CoA) reductase and increasing the number of hepatic low-density lipoprotein receptors. A concomitant increase in very low-density lipoprotein synthesis can occur. These compensatory effects result in increased clearance of LDL-C from the blood, resulting in decreased serum LDL-C levels.
In a 6-month dose-response study in patients with primary hypercholesterolemia receiving 3.8 or
4.5 g colesevelam, a 15 to 18% decrease in LDL-C levels were observed, which was evident within 2 weeks of administration. In addition, total-C decreased 7 to 10%, HDL-C increased 3% and triglycerides increased 9 to 10%. Apo B decreased by 12%. In comparison, in patients given placebo, LDL-C, total-C, HDL-C and apo-B were unchanged, while triglycerides increased 5%. Studies examining administration of colesevelam as a single dose with breakfast, a single dose with dinner, or as divided doses with breakfast and dinner did not show significant differences in LDL-C reduction for different dosing schedules. However, in one study triglycerides tended to increase more when colesevelam was given as a single dose with breakfast. Multicentre, randomized, double-blind, placebo-controlled studies in 487 patients demonstrated an additive reduction of 8 to 16% in LDL-C when 2.3 to 3.8 g colesevelam and a statin (atorvastatin, lovastatin or simvastatin) were administered at the same time. Initiation of add-on treatment with colesevelam subsequent to statin therapy has not been specifically studied. Colesevelam has not been compared directly to other bile acid sequestrants in clinical trials.
In a 6-week study 129 patients with mixed hyperlipidemia were randomized to fenofibrate 160 mg plus 3.8 g colesevelam or fenofibrate alone. The fenofibrate plus colesevelam group (64 patients) demonstrated a 10% reduction in LDL-C levels versus 2% increase for the fenofibrate group (65 patients). Reductions were also seen for non-HDL-C, total-C and apo-B. A small 5%, non-significant increase in triglycerides was noted. The effects of combination of fenofibrate and colesevelam on the risks of myopathy or hepatotoxicity are not known.
Pharmacokinetics
Colesevelam is not absorbed from the gastrointestinal tract.
Absorption
Colesevelam hydrochloride is a hydrophilic, water-insoluble polymer that is not hydrolyzed by digestive enzymes and is not absorbed.
Distribution
Colesevelam hydrochloride is not absorbed, and therefore, its distribution is limited to the gastrointestinal tract.
Metabolism
Colesevelam hydrochloride is not metabolized systemically and does not interfere with systemic drug-metabolizing enzymes such as cytochrome P-450.
Excretion
In 16 healthy volunteers, an average of 0.05% of administered radioactivity from a single 14C- labeled colesevelam hydrochloride dose was excreted in the urine.
STORAGE AND STABILITY
Store between 15-30°C. Protect from moisture.
SPECIAL HANDLING INSTRUCTIONS
No special requirements. Keep out of reach and sight of children.
DOSAGE FORMS, COMPOSITION AND PACKAGING
JAMP Colesevelam (colesevelam) 625 mg is film-coated tablets. Each tablet contains 625 mg of colesevelam hydrochloride. Off white to light yellow, capsule shaped coated tablets imprinted with “C625” in black ink on one side and plain on other side.
Tablet core:
Colloidal silicon dioxide, hypromellose, magnesium stearate and microcrystalline cellulose
Film-coating:
Hypromellose and polyethylene glycol
Printing ink:
Ammonium hydroxide, iron oxide black, propylene glycol and shellac
Available in HDPE bottles of 180 tablets with child resistant cap.
PART II: SCIENTIFIC INFORMATION
PHARMACEUTICAL INFORMATION
Drug Substance
Common name: Colesevelam Hydrochloride
Chemical name: 1-Hexaminium, N,N,N-Trimethyl-6-(2-propenylamino)-, chloride, polymer with (chloromethyl) oxirane, 2-propen-4-amine and N-2-propenyl-1-decanamine, hydrochloride
Molecular formula: (C3H8NCl)2(C9H20N2OCl2)1(C13H28NCl)7(C12H28N2Cl2)6
Molecular weight: 212 g/mol
Structural formula:
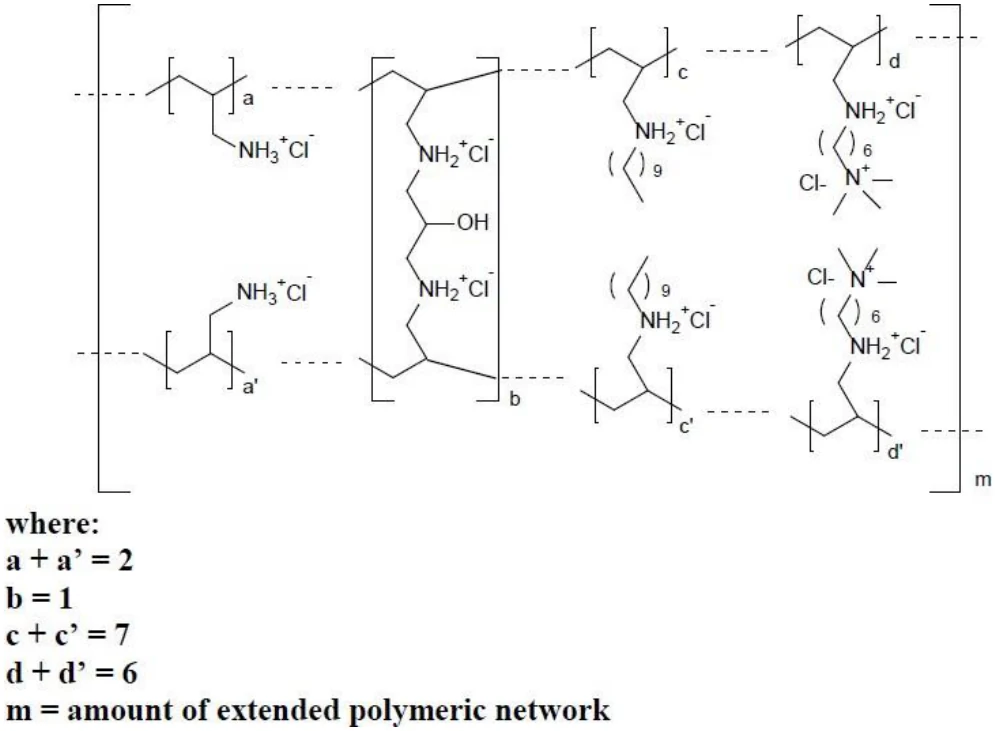
Colesevelam hydrochloride is achiral.
Physicochemical properties:
Physical description: Colesevelam hydrochloride is off-white to light yellow powder.
Physical form: Solid
Solubilities: Insoluble in all aqueous and organic solvents.
pH and pKa values: The pH value is not applicable because colesevelam hydrochloride is water insoluble.
CLINICAL TRIALS
Comparative Bioavailability Studies
Colesevelam hydrochloride resin is not absorbed from the gastrointestinal (GI) tract but passes through the GI tract and complexes with bile acids. The complexes are then excreted with unchanged resin in the feces. Consequently, conventional comparative bioavailability studies are not considered to be a valid test of product performance for the purpose of demonstrating bioequivalence.
Comparative in vitro equilibrium and kinetic binding studies with bile acids were conducted in order to demonstrate bioequivalence between JAMP Colesevelam film coated tablets 625 mg (JAMP Pharma Corporation, Canada) and PrLodalisTM/MC colesevelam hydrochloride tablets 625 mg (Valeant Canada, Laval Quebec H7L 4A8).
Twelve randomized, placebo-controlled efficacy studies were conducted in 1,740 patients with hyperlipidemia. A total of 1,193 patients were treated with colesevelam: 807 received colesevelam alone, 279 received a colesevelam /HMG-CoA reductase inhibitor combination, and 107 received colesevelam combined with another lipid lowering agent.
Colesevelam administered alone or with a statin was shown to be effective in reducing LDL-C and total-C and in increasing HDL-C in patients with primary hypercholesterolemia.
Study demographics and trial design
The patient population included men and women 18 years of age or older with primary hypercholesterolemia. The mean age was 56 years; 51% of the population was male. Patients had a serum LDL-cholesterol of at least 3.36 mmol/L. All patients followed a low-fat, low-cholesterol diet, avoided fasting or binge eating, and ate at least 2 meals on most days.
All studies were randomized, placebo-controlled, double-blind, parallel-group studies; eight of the studies had an active control group (Table 4).
Table 4 - Summary of Design and Patient Demographics for all Efficacy Studies
| Study # | Design | Route of administration and duration | Dosage | Study subjects (n) | Mean age (Range) | Percent male |
| GTC-37- 201 | Randomized DB, PC, PG | p.o. 6 weeks | Placebo 0.8 g bid 1.2 g bid 1.6 g bid 2.0 g bid | 29 30 30 31 29 | 56.0 y (31-80) | 44% |
| GTC-37- 202 | Randomized DB, PC, PG | p.o. 4 weeks | Placebo 1.6 g q AM 1.6 g q PM 0.8 g bid | 32 30 30 30 | 55.4 y (21-83) | 57% |
| GTC-37- 203 | Randomized DB, PC, PG | p.o. 4 weeks | Placebo 2.4 g q PM Lovastatin 10 mg q PM 2.4 g q PM + lovastatin 10 mg q PM 2.4 g q PM + lovastatin 10 mg q HS | 26 29 26 29 25 | 57.7 y (23-88) | 45% |
| GTC-48- 204 | Randomized DB, PC, PG | p.o. 6 weeks | Placebo 1.2 g bid 2.0 g bid Simvastatin 10 mg q.d Simvastatin 20 mg q.d 1.2 g bid + simvastatin 20 mg q.d 2.0 g bid + simvastatin 10 mg q.d | 35 38 38 36 39 37 35 | 54.3 y (18-82) | 58% |
| GTC-48- 205 | Randomized DB, PC, PG | p.o. 4 weeks | Placebo 2.0 g bid Atorvastatin 10 mg q.d 2.0 g bid + atorvastatin 10 mg q.d Atorvastatin 80 mg q.d | 19 17 19 19 20 | 57.3 y (28-79) | 70% |
| GTC-48- 301 | Randomized DB, PC, PG | p.o. 6 months | Placebo 1.2 g bid 1.6 g bid 2.0 g bid 2.4 g bid | 94 102 98 101 99 | 55.5 y (18-86) | 50% |
| GTC-48- 302 | Randomized DB, PC, PG | p.o. 6 weeks | Placebo 4.0 g q AM 4.0 g q PM 2.0 g bid | 23 27 24 24 | 55.2 y (24-70) | 45% |
| WEL-403 | Randomized DB, PC, PG | p.o. 6 weeks | 3.75 g q.d + fenofibrate 160 mg q.d Placebo + fenofibrate 160 mg q.d | 64 65 | 54.8 y (31-70) | 56% |
| Study # | Design | Route of administration and duration | Dosage | Study subjects (n) | Mean age (Range) | Percent male |
| WEL-405 | Randomized DB, PC, PG | p.o. 6 weeks | 3.75 g q.d + simvastatin Simvastatin mean of 28 mg/day | 47 25 | 60 y (31-82) | 50% |
| WEL-406 | Randomized DB, PC, PG | p.o. 6 weeks | 3.75 g q.d + atorvastatin Atorvastatin mean of 16 mg/day | 40 25 | 57.7 y (32-78) | 44% |
| WEL-407 | Randomized DB, PC, PG | p.o. 6 weeks | 3.75 g q.d + pravastatin Pravastatin mean of 25 mg/day | 47 20 | 54.8 y (29-80) | 40% |
| WEL-408 | Randomized DB, PC, PG | p.o. 10 weeks | 3.75 g q.d + ezetimibe 10 mg/day Placebo + ezetimibe 10 mg/day | 43 43 | 59.1 y (24-79) | 43% |
Monotherapy
The efficacy and safety of colesevelam monotherapy was evaluated in seven randomized, double-blind, placebo-controlled studies (Table 5). Three of these studies included an active control of atorvastatin, pravastatin, or simvastatin.
Study results
The primary efficacy parameter in all of the studies was the percent change in serum LDL cholesterol concentration from the end of the diet period to the end of an active treatment period. Secondary efficacy variables included the percent change in total cholesterol, HDL cholesterol, and triglycerides.
Compared to baseline, colesevelam reduced LDL-C at all doses studied, whether taken as a single daily dose or as divided doses. In dose-ranging studies, there was a clear dose-response relationship over the range of doses studied. The decreases were greater than on placebo at all doses studied. In the largest phase 3 study, all pairwise comparisons were significant except for 12 g bid compared to 1.6 g bid and 1.6 g bid compared to 2.0 g bid. In studies with an active control, HMG-CoA reductase inhibitor resulted in a greater reduction of LDL-C than did colesevelam.
Colesevelam also reduced total cholesterol and tended to increase HDL-C and triglycerides.
A maximum therapeutic response to colesevelam was generally achieved within 2 weeks and was maintained during long-term therapy.
Colesevelam is equally effective in a variety of patient populations with hypercholesterolemia: men and women, under or over 65 years of age, pre- and post-menopausal women, Caucasians and non- Caucasians.
Table 5 - Summary of Monotherapy Study Results (mean % change from baseline)
| Study | LDL-C | TOT-C | HDL-C | TG | ||||
| Treatment | % Δ | p | % Δ | p | % Δ | p | % Δ | p |
| GTC-37-201 | ||||||||
| Placebo | 1.36 | 0.3910 | 0.52 | 0.6158 | -1.11 | 0.5088 | -0.20 | 0.9673 |
| 0.8 g bid | -4.24 | 0.0328 | -2.16 | 0.0829 | 3.27 | 0.2304 | 3.34 | 0.3819 |
| 1.2 g bid | -7.63 | 0.0002 | -5.1 | 0.0008 | 0.82 | 0.6324 | 1.85 | 0.7151 |
| 1.6 g bid | -11.46 | 0.0001 | -7.55 | 0.0001 | 4.1 | 0.0649 | 4.84 | 0.3980 |
| 2.0 g bid | -15.21 | 0.0001 | -7.53 | 0.0001 | 4.71 | 0.0348 | 23.14 | 0.0212 |
| GTC-37-202 | ||||||||
| Placebo | 1.27 | 0.5062 | 1.1 | 0.4433 | -0.76 | 0.7056 | 4.91 | 0.3734 |
| 1.6 g q AM | -7.23 | 0.0002 | -2.84 | 0.0242 | 1.97 | 0.2714 | 21.20 | 0.0050 |
| 1.6 g q PM | -7.18 | 0.0001 | -3.78 | 0.0087 | 2.1 | 0.2334 | 9.06 | 0.1348 |
| 0.8 g bid | -6.31 | 0.0004 | -4.48 | 0.0045 | 0.49 | 0.8175 | 0.79 | 0.8313 |
| GTC-37-203 | ||||||||
| Placebo | 0.5 | 0.8297 | 0.6 | 0.7015 | 1.2 | 0.5207 | 2.00 | 0.5934 |
| 2.4 g q PM | -6.9 | 0.0064 | -2.6 | 0.1076 | 4.6 | 0.0041 | 14.20 | 0.0013 |
| Lovastatin 10 mg q PM | -22.5 | <0.0001 | -14.5 | <0.0001 | 3.2 | 0.0917 | 5.40 | 0.3819 |
| GTC-48-204 | ||||||||
| Placebo | -3.7 | 0.0044 | -2.2 | 0.0906 | -2.2 | 0.2219 | 5.50 | 0.2553 |
| 1.2 g bid | -8.5 | <0.0001 | -3.9 | 0.0047 | 4.3 | 0.0043 | 12.60 | 0.0963 |
| 2.0 g bid | -16 | <0.0001 | -9 | <0.0001 | 1.9 | 0.3000 | 15.00 | 0.0070 |
| Simvastatin 10 mg q.d | -25.5 | <0.0001 | -18.7 | <0.0001 | 4.9 | 0.0177 | -11.60 | 0.0112 |
| Simvastatin 20 mg q.d | -33.8 | <0.0001 | -23.4 | <0.0001 | 6.5 | 0.0010 | -9.70 | 0.0028 |
| GTC-48-205 | ||||||||
| Placebo | -0.6 | 0.2753 | 1.1 | 0.0434 | 4.4 | 0.0494 | 9.50 | 0.1956 |
| 2.0 g bid | -12.5 | 0.0021 | -5.9 | 0.0182 | 2.7 | 0.0067 | 9.90 | 0.1754 |
| Atorvastatin 10 mg q.d | -38.5 | <0.0001 | -28.9 | <0.0001 | 8.3 | 0.0093 | -24.40 | 0.0268 |
| GTC-48-301 | ||||||||
| Placebo | 0.8 | 0.7905 | 0.6 | 0.3091 | -1.1 | 0.2681 | 4.60 | 0.0701 |
| 1.2 g bid | -9.3 | <0.0001 | -4.9 | <0.0001 | 2.6 | 0.0003 | 8.60 | 0.0022 |
| 1.6 g bid | -12.4 | <0.0001 | -6.2 | <0.0001 | 3.9 | <0.0001 | 4.80 | 0.0148 |
| 2.0 g bid | -16.3 | <0.0001 | -8.1 | <0.0001 | 2.9 | 0.0001 | 9.90 | <0.0001 |
| 2.4 g bid | -19.6 | <0.0001 | -10.3 | <0.0001 | 2.6 | 0.0003 | 9.40 | 0.0017 |
| GTC-48-302 | ||||||||
| Placebo | 0.8 | 0.7729 | 2 | 0.6261 | 1.9 | 0.4477 | 9.60 | 0.5604 |
| 4.0 g q AM | -18.4 | <0.0001 | -9.3 | 0.0002 | 3 | 0.4091 | 25.40 | 0.0031 |
| 4.0 g q PM | -13.9 | <0.0001 | -7 | 0.0002 | 7.5 | 0.0022 | 12.20 | 0.1014 |
| 2.0 g bid | -18.4 | <0.0001 | -9.3 | <0.0001 | 9.5 | 0.0010 | 9.40 | 0.0717 |
Combination Therapy
Colesevelam was co-administered with an HMG-CoA reductase inhibitor (atorvastatin, lovastatin, pravastatin, or simvastatin) in 6 clinical studies. Combination therapy resulted in an additive effect on LDL-C.
Each of the lovastatin-colesevelam combination therapies in study 37-203 reduced LDL-C to a greater extent than either lovastatin or colesevelam alone (p<0.005); the combination therapy groups did not differ from each other (p=0.480). In study 37-204, LDL-C decreased more in each simvastatin-colesevelam combination therapy group compared to each simvastatin group (p<0.006); there was no difference between the two simvastatin groups (p=0.0546) or between the two combination therapy groups (p=0.674). The decrease in LDL-C in study 34-205 was greater after treatment with the combination atorvastatin-colesevelam than after treatment with atorvastatin 10 mg alone (p=0.007), but not different from atorvastatin 80 mg alone (p=0.070).
In studies WEL-405, WEL-406, and WEL-407, the patients were first stabilized on an individualized dose of the statin before randomization. In study WEL-405, LDL-C did not change in the active control group (p=0.763); LDL-C decreased more on the combination simvastatin- colesevelam than on simvastatin alone (p=0.0003). In the two other studies, the decreases in LDL-C in the combination therapy groups were similar to that seen in the combination therapy group in study WEL-403, but there were also unexpected smaller decreases in LDL-C in the control groups.
Table 6 - Summary of Combination Therapy Study Results (mean % change from baseline)
| Study | LDL-C | TOT-C | HDL-C | TG | |||||||||
| Treatment | % Δ | p | % Δ | p | % Δ | p | % Δ | p | |||||
| GTC-37-203 | |||||||||||||
| Lovastatin 10 mg q PM | -22.5 | <0.0001 | -14.5 | <0.0001 | 3.2 | 0.0917 | 5.4 | 0.3819 | |||||
| 2.4 g q PM + lovastatin 10 mg q PM | -34.0 | <0.0001 | -20.8 | <0.0001 | 3.4 | 0.1 | 8.6 | 0.2173 | |||||
| 2.4 g q PM + lovastatin 10 mg q HS | -31.8 | <0.0001 | -21 | <0.0001 | 3.1 | 0.0788 | -2.9 | 0.4879 | |||||
| GTC-48-204 | |||||||||||||
| Simvastatin 10 mg q.d | -25.5 | <0.0001 | -18.7 | <0.0001 | 4.9 | 0.0177 | -11.6 | 0.0112 | |||||
| Simvastatin 20 mg q.d | -33.8 | <0.0001 | -23.4 | <0.0001 | 6.5 | 0.001 | -9.7 | 0.0028 | |||||
| 1.2 g bid + simvastatin 20 mg q.d | -42.3 | <0.0001 | -29.1 | <0.0001 | 6.1 | 0.0017 | -4.8 | 0.0493 | |||||
| 2.0 g bid + simvastatin 10 mg q.d | -41.5 | <0.0001 | -28.3 | <0.0001 | 10.2 | <0.0001 | -3.2 | 0.2013 | |||||
| GTC-48-205 | |||||||||||||
| Atorvastatin 10 mg q.d | -38.5 | <0.0001 | -28.9 | <0.0001 | 8.3 | 0.0093 | -24.4 | 0.0268 | |||||
| 2.0 g bid + atorvastatin 10 mg q.d | -49.1 | <0.0001 | -28 | <0.0001 | 10.8 | 0.001 | -1.3 | 0.865 | |||||
| Atorvastatin 80 mg q.d | -56.3 | <0.0001 | -42.4 | <0.0001 | 5.5 | 0.0336 | -32.8 | <0.0001 | |||||
| WEL-405 | 0 | ||||||||||||
| Simvastatin mean of 28 mg q.d | -1.1 | 0.7626 | -0.7 | 0.7819 | 1 | 0.6676 | 2.1 | 0.9223 | |||||
| 3.75 g q.d + simvastatin | -18.6 | <0.0001 | -8.2 | <0.0001 | 2 | 0.2459 | 17.8 | 0.5774 | |||||
| WEL-406 | |||||||||||||
| Atorvastatin mean of 16 mg q.d | -13.5 | 0.0004 | -6.6 | 0.0089 | -1 | 0.6539 | 9.4 | 0.7751 | |||||
| 3.75 g q.d + atorvastatin | -17.2 | <0.0001 | -8.4 | <0.0001 | 1 | 0.5599 | 15.5 | 0.6256 | |||||
| WEL-407 | |||||||||||||
| Pravastatin mean of 25 mg q.d | -4.7 | 0.2320 | -3 | 0.1895 | -1.1 | 0.6382 | 4.7 | 0.8074 | |||||
| 3.75 g q.d + pravastatin | -11.9 | 0.0001 | -5.3 | 0.0010 | -2.5 | 0.1485 | 16.4 | 0.6589 | |||||
DETAILED PHARMACOLOGY
Colesevelam hydrochloride is a novel polymeric substance designed to be administered orally to sequester bile acids and reduce their reabsorption.
Colesevelam hydrochloride was designed to incorporate both ionic and hydrophobic characteristics into the polymer in a pattern that would be complementary to the ionic and hydrophobic characteristics of bile acids. The resulting polymer should allow for enhanced binding of trihydroxy bile acids such as cholic acid as well as sufficiently tight binding to allow for retention of bile acids as they pass through the colon. Studies were conducted to confirm in vitro and in vivo binding to bile acids.
The physical chemical properties of colesevelam hydrochloride are such that it is unlikely to be absorbed after oral administration as confirmed by [14C]- studies in rats, dogs and humans.
Recovery of radiolabel was complete in the rat study and in one dog study, but only 75-80% in the other dog study and in the human studies. In none of the studies was there evidence of the [14C]- labeled material in tissues or plasma. Since colesevelam hydrochloride is not absorbed, no metabolism or distribution studies were conducted.
Findings in rats, dogs and man correlated well. The high doses administered to laboratory species resulted in reductions in plasma concentrations of fat-soluble vitamins. However, assays of fat- soluble vitamins in human studies did not indicate any evidence of reductions.
Pharmacological studies confirmed that colesevelam hydrochloride binds bile acids in man, hamsters and rats, and reduces plasma cholesterol in man and dogs (but not in rats).
TOXICOLOGY
General Toxicology Studies
Colesevelam hydrochloride was tolerated after daily oral dosing of up to 2 g/kg/day (32 times human maximal dose based on a mg/kg basis) for 52 weeks in dogs and in rats after 1.2 g/kg/day (19 times human dose) for 6 months. In dogs, treatment at 0.67 and 2 g/kg resulted in discolored feces and mucoid discharge. There were local gastrointestinal effects in some dogs which may be related to the large amount of administered compound. After 2.4 g/kg/day for 5 weeks, male rats died secondary to hemorrhage, presumed to be secondary to reduced vitamin K absorption.
Lifetime administration (2 year) in rodents (rat and mice) were conducted with diet supplemented with vitamins and doses of 2.4 g/kg/day and 3 g/kg/day were tolerated. Serum vitamin K levels were not determined in repeat dose studies in rats, but serum levels of vitamin D and E were decreased in rat at 1.2 mg/kg and at 0.6 mg/kg in the dog. Thus, for chronic administration, careful attention has to be paid to effect secondary to reduced uptake of fat-soluble vitamins.
Reproductive Toxicology Studies
Colesevelam hydrochloride had no effects on male or female fertility or early embryonic development in male and female rats administered 2 g/kg/day (approximately 32 times the maximum human dose, based on body weight, mg/kg) orally prior to and during mating and early pregnancy.
Colesevelam hydrochloride administered orally during organogenesis at doses up to 3 g/kg/day and 1 g/kg/day in rats and rabbits, respectively (approximately 48 and 16 times the maximum human dose, based on body weight, mg/kg) and have revealed no evidence of harm to the fetus. There were no effects on pre- and post-natal development in rats treated with colesevelam hydrochloride from gestation day 6 through lactation day 20 at doses up to 1 g/kg.
Carcinogenesis: A 104-week carcinogenicity study with colesevelam hydrochloride was conducted in CD-1 mice (n=50 per sex per dose group), at oral dietary doses up to 3 g/kg/day. Cholangioma (bile duct adenoma) was noted only at the mid-dose (1 male at 1 g/kg/day; 16 times the maximum recommended human dose of 4.5 g/day, based on body weight, mg/kg) and at the high dose (1 male and 1 female at 3 g/kg/day; 48 times the maximum recommended human dose of 4.5 g/day, based on body weight). This is a spontaneous but uncommon tumor in mice. The relevance of this finding to humans has not been established. In a 104-week carcinogenicity study with colesevelam hydrochloride in Harlan Sprague-Dawley rats, a statistically significant increase in the incidence of pancreatic acinar cell adenoma was seen in male rats at doses >1.2 g/kg/day (approximately 19 times the maximum human dose, based on body weight, mg/kg) (trend test only). A statistically significant increase in thyroid C-cell adenoma was seen in female rats at 2.4 g/kg/day (approximately 40 times the maximum human dose, based on body weight, mg/kg).
Mutagenesis: Colesevelam hydrochloride and 4 degradants present in the drug substance have been evaluated for mutagenicity in the Ames test and a mammalian chromosomal aberration test. The 4 degradants and an extract of the parent compound did not exhibit genetic toxicity in an in vitro bacterial mutagenesis assay in S. typhimurium and E. coli (Ames assay) with or without rat liver metabolic activation. An extract of the parent compound was positive in the Chinese Hamster Ovary (CHO) cell chromosomal aberration assay in the presence of metabolic activation and negative in the absence of metabolic activation. The results of the CHO cell chromosomal aberration assay with 2 of the 4 degradants, decylamine HCl and aminohexyltrimethyl ammonium chloride HCl, were equivocal in the absence of metabolic activation and negative in the presence of metabolic activation. The other 2 degradants, didecylamine HCl and 6-decylamino-hexyltrimethyl ammonium chloride HCl, were negative in the presence and absence of metabolic activation.
REFERENCES
- 1. Avorn J, Monette J, Lacour A, et al. Persistence of use of lipid-lowering medications: a cross-national study. JAMA. 1998;279:1458-62.
- 2. Expert Panel. Report of the National Cholesterol Education Program Expert Panel on Detection, Evaluation, and Treatment of High Blood Cholesterol in Adults. Arch Intern Med. 1988;148:36-69.
- 3. Brown MS, Goldstein, J.L. Drugs used in the treatment of hyperlipoproteinemias. In: Goodman LS, Gilman, A., ed. The Pharmacologic Basis of Therapeutics. 8 ed. New York: TMGraw-Hill Book Co.; 1990:874-96.
- 4.
Levine GN, et al. Cholesterol reduction in cardiovascular disease. New Engl. J. Med.
1995;332:512-21.
- 5. Eisenberg DA. Cholesterol lowering in the management of coronary artery disease: the clinical implications of recent trials. Am J Med. 1998;104:2S-5S.
- 6. Gotto AM, Jr. Lipid lowering and coronary risk. Isr J Med Sci. 1996;32:355-9.
- 7. Lipid Research Clinic Program. The Lipid Research Clinics Coronary Primary Prevention Trial results. II. The relationship of reduction in incidence of coronary heart disease to cholesterol lowering. JAMA. 1984;251:365-74.
- 8. Rossouw JE. The effects of lowering serum cholesterol on coronary heart disease risk. Med Clin North Am. 1994;78:181-95.
- 9. Law MR, Wald NJ, Thompson SG. By how much and how quickly does reduction in serum cholesterol concentration lower risk of ischaemic heart disease? Br. Med. J. 1994;308:367- 72.
- 10. TMPherson R, et al. Canadian Cardiovascular Society position statement - Recommendations for the diagnosis and treatment of dyslipidemia and prevention of cardiovascular disease. Can J Cardiol 2006; 22 (11); 913-927.
- 11. Graham I, et al. European Guidelines on cardiovascular disease prevention in clinical practice: Executive summary. Atheroscelerosis 2007; 197; 1-45.
- 12. Jelinek DF, Andersson S, Slaughter CA, Russell DW. Cloning and regulation of cholesterol 7 alpha-hydroxylase, the rate- limiting enzyme in bile acid biosynthesis. J Biol Chem. 1990;265:8190-7.
- 13.
Illingworth DR. New horizons in combination drug therapy for hypercholesterolemia.
Cardiology. 1989;76:83-94; discussion -100.
- 14. Setchell KDR, Street JM, Sjövall J. Fecal bile acids. In: Setchell KDR, Kritchevsky D, Nair PP, eds. The Bile Acids. Chemistry, Physiology, and Metabolism. New York: Plenum Press; 1988:441-570.
- 15.
Czubayko F, Beumers B, Lammsfuss S, Lutjohann D, von Bergmann K. A simplified
micro-method for quantification of fecal excretion of neutral and acidic sterols for outpatient studies in humans. J Lipid Res. 1991;32:1861-7.
- 16. Lindenthal B, Simatupang A, Dotti MT, Federico A, Lutjohann D, von Bergmann K. Urinary excretion of mevalonic acid as an indicator of cholesterol synthesis. J Lipid Res. 1996;37:2193-201.
- 17. Wasserhess P, Becker M, Staab D. Effect of taurine on synthesis of neutral and acidic sterols and fat absorption in preterm and full-term infants. Am J Clin Nutr. 1993;58:349-53.
- 18. Rossi SS, Wayne ML, Smith RB, Wright CE, Andreadis NA, Hofmann AF. Effect of the bile-acid sequestrant colestipol on postprandial serum bile-acid concentration: evaluation by bioluminescent enzymic analysis. Aliment Pharmacol Ther. 1989;3:41-6.
- 19. Knapp HH, Schrott H,Ma P, Knopp R, Chin B. Gaziano JM, Donovan JM, Burke S, Davidson M. Efficacy and safety of combination simvastatin and colesevelam in patients with Primary hypercholesterolemia. Am J Med. 2001;110: 352-360.
- 20. Hunninghake D, Insull W, Toth P, Davidson D, Donovan JM, Burke SK. Coadministration of colesevelam hydrochloride with atorvastatin lowers LDL cholesterol additively. Atherosclerosis. 2001; 158:407-416.
- 21. Bays H, Rhyne J, Abby S, Lai Y, Jones M. Lipid-lowering effects of colesevelam HCl in combination with ezetimibe. Current Medical Research Opinion. 2006; 11:2191-2200.
- 22. Insull W. Clinical utility of bile acid sequestrants in the treatment of dyslipidemia: a scientific review. Southern Med J. 2006; 99(3): 257-273.
- 23. Corsini, A. Colesevelam hydrochloride: usefulness of a specifically engineered bile acide sequesterant for lowering LDL-cholesterol. European Journal of Cardiovascular Prevention &Rehabilitation. Feb 2009.
- 24. TMKenney J, Jones M, Abby S. Safety and efficacy of colesevelam hydrochloride in combination with fenofibrate for the treatment of mixed hyperlipodemia. Current Medical Research Opinion. 2005;21:9:1403-1412.
- 25. Corsini A, Eberhard W, Farnier, Colesevelam hydrochloride: usefulness of a specifically engineered bile acid sequestrant for lowering LDL-cholesterol. European Journal of Cardiovascular Prevention & Rehabilitation. 2009;16:1-9.
- 26. Studer M, Briel M, Leimenstoll B, Glass TR, Bucher HC. Effect of different antilipidemic agents and diets on mortality. Arch Intern Med. 2005;165:725-730.
- 27. Grundy SM, Cleeman JI, Merz CNB, Brewer HB, Clark LT, Hunninghake DB, Pasternak RC, Smith SC, Stone NJ. Implications of recent clinical trials for the national cholesterol education program adult treatment panel III guidelines. Arterioscler Thromb Vasc Biol. 2004;24:e149-e161.
- 28. Braunlin W, Zhorov E, Smisek D, Guo A, Appruzese W, Xu Q, Hook P, Holmes-Farley R, Mandeville. In vitro comparison of bile acid binding to colesevelam HCl and other bile acid sequestrants. Polymer preprints. 2000;41(1):708-709.
- 29. Bays H, Dujovne C. Colesevelam HCl: a non-systemic lipid-altering drug. Expert Opin. Pharmacother.2003;4(5):779-790.
- 30. Holmes-Farley SR, Mandeville WH, Miller KL, Petersen J, Ward J, Sacchiero B, Maloney C, Brochi S, Rosenbaum D, Goldberg D, Norton KA, Chen X, Mazzeo JR. Colesevelam hydrochloride:synthesis and testing of a novel polymer gel pharmaceutical. Poylmer preprints. 2000;41(1):735-736.
- 31. Davidson MH, Dicklin MR, Maki KC, Kleinpell RM. Colesevelam hydrochloride: a non- absorbed, polymeric cholesterol-lowering agent. Exp. Opin. Invest. Drugs. 2000;9(11):2663- 2671.
- 32. Heller DP, Burke SK, Davidson DM, Donovan JM. Absorption of colesvelam hydrochloride in healthy volunteers. Ann Pharmacother.2002;36:398-403.
- 33. Insull W, Toth P, Mullican W, Hunninghake D, Burke S, Donovan JM, Davidson MH. Effectiveness of colesevelam hydrochloride in decreasing LDL cholesterol in patients with primary hypercholesterolemia: a 24-week randomized controlled trial. Mayo Clin Proc.2001;76:971-982.
- 34.
Steinmetz KL, Schonder KS. Colesevelam: Potential uses for the newest bile resin.
Cardiovascular Drug Reviews.2005;23(1):15-30.
- 35. Bays HE., Goldberg RB. The Forgotten Bile Acid Sequestrants: Is Now a Good Time to Remember? American Journal of Therapeutics. 2007; 14: 567-580.
- 36. PrLODALISTM, (film-coated tablets, 625 mg and powder for oral suspension, 3.75 g), control 241993, Product Monograph, Bausch Health, Canada Inc. (DEC 4, 2020)